Poll Finding

KFF Health Tracking Poll: Public Weighs Political Consequences of Health Policy Legislation

Published: Oct 3, 2025

Key Takeaways

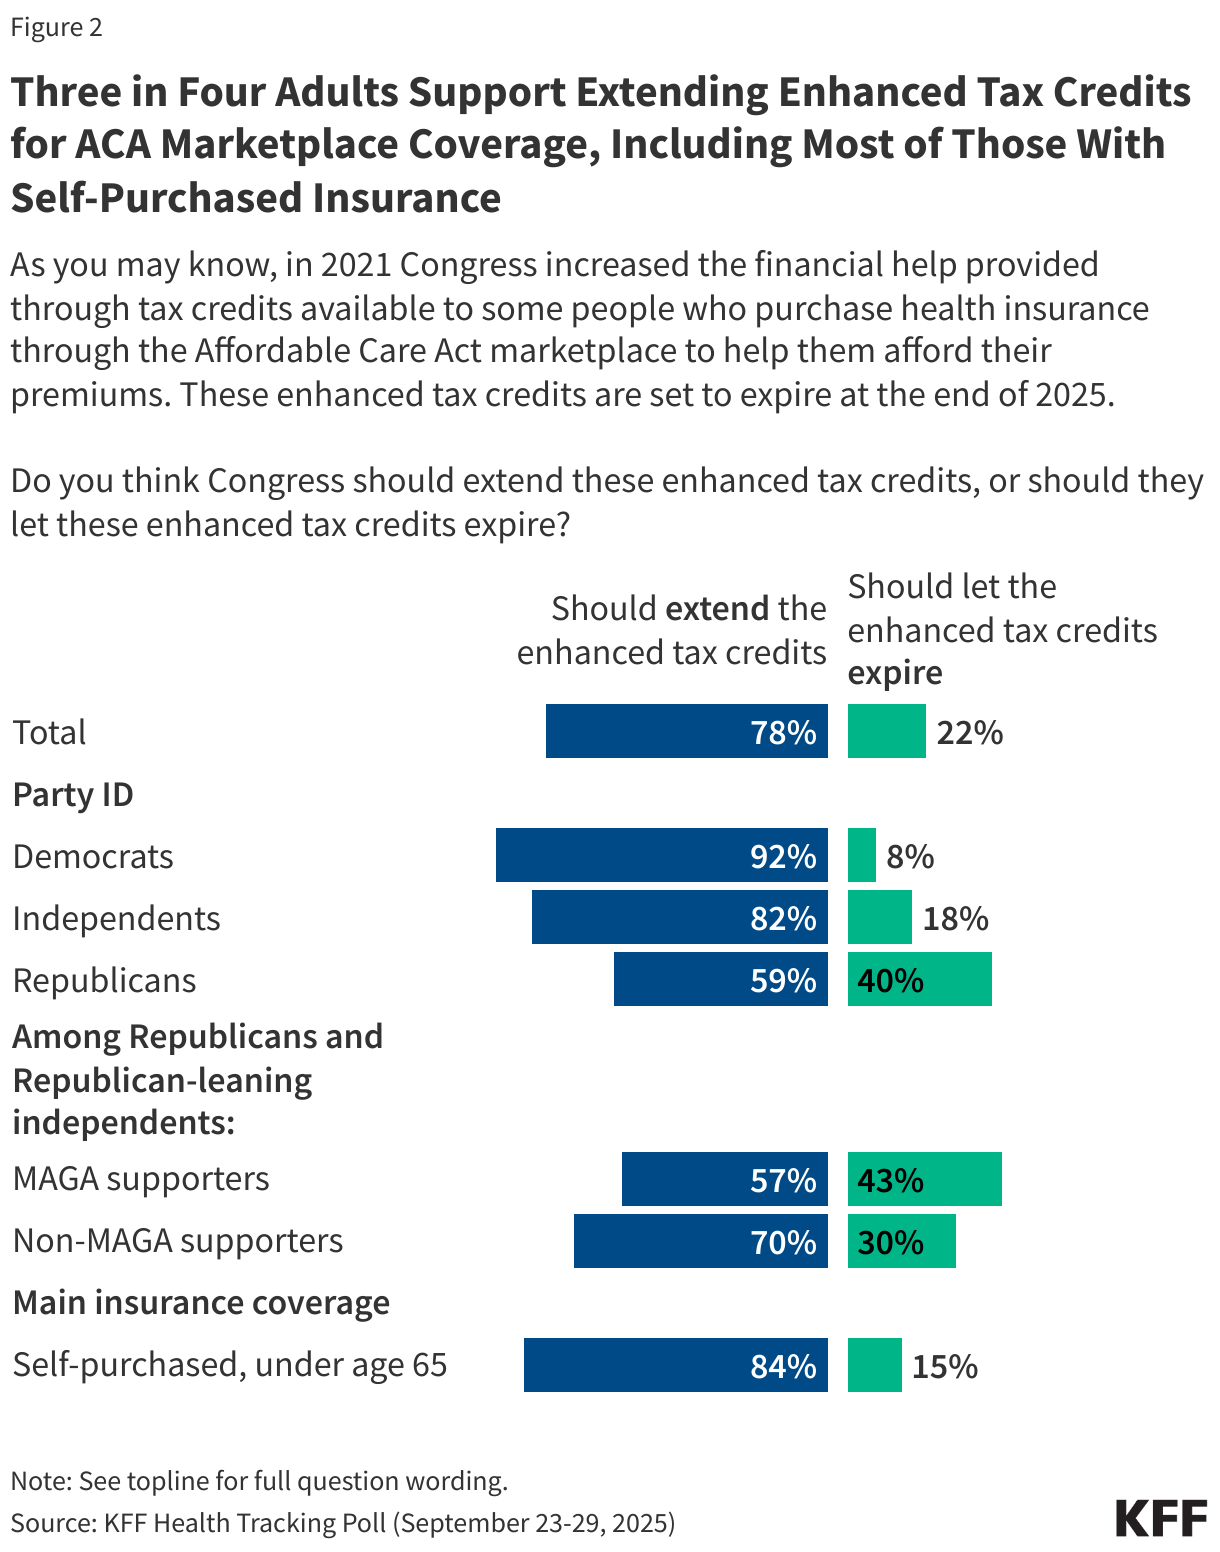
  • As Congress debates federal health care spending as part of spending bill negotiations, including extending the enhanced premium tax credits, the latest KFF Health Tracking Poll finds three-quarters (78%) of adults say Congress should extend the enhanced tax credits for people who buy their own insurance through the ACA Marketplace. This is more than three times the share of the public (22%) who say Congress should let the credits expire. Notably, majorities across political party want Congress to extend the tax credits including nine in ten (92%) Democrats, eight in ten (82%) independents, and six in ten (59%) Republicans. A majority of Republicans who align with the MAGA movement (57%) also say Congress should extend these subsidies.
  • Both parties could face political fallout if the enhanced tax credits are not extended, though the public says they will place most of the blame on those currently in charge. About four in ten (39%) adults who want to see the tax credits extended say that if Congress does not extend these enhanced tax credits, President Trump deserves most of the blame, while another four in ten (37%) say the same about Republicans in Congress. About two in ten (22%) say that Democrats in Congress deserve most of the blame. Democrats are most likely to place blame on President Trump (56%) followed by Republicans in Congress (42%), while six in ten Republicans (61%) say they would place the blame on Democrats in Congress. Among those who buy their own coverage (nearly half of whom identify as Republican or Republican-leaning), Republicans in Congress and President Trump receive the majority of the blame (42% and 37%, respectively). 
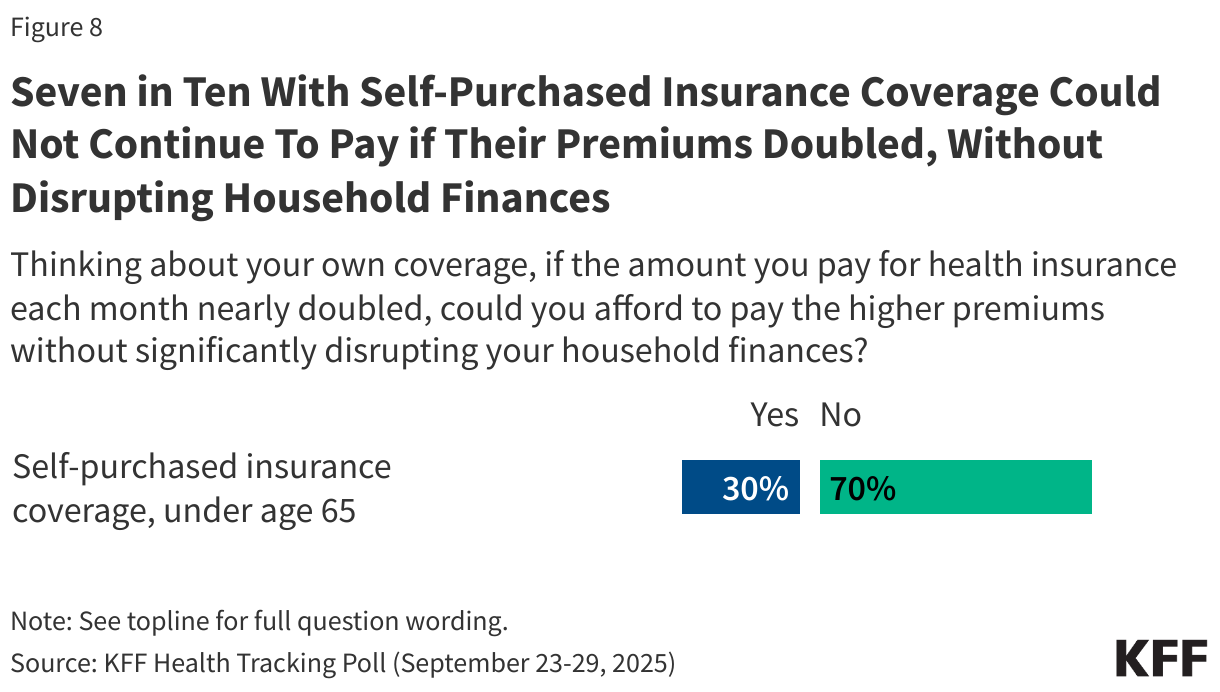
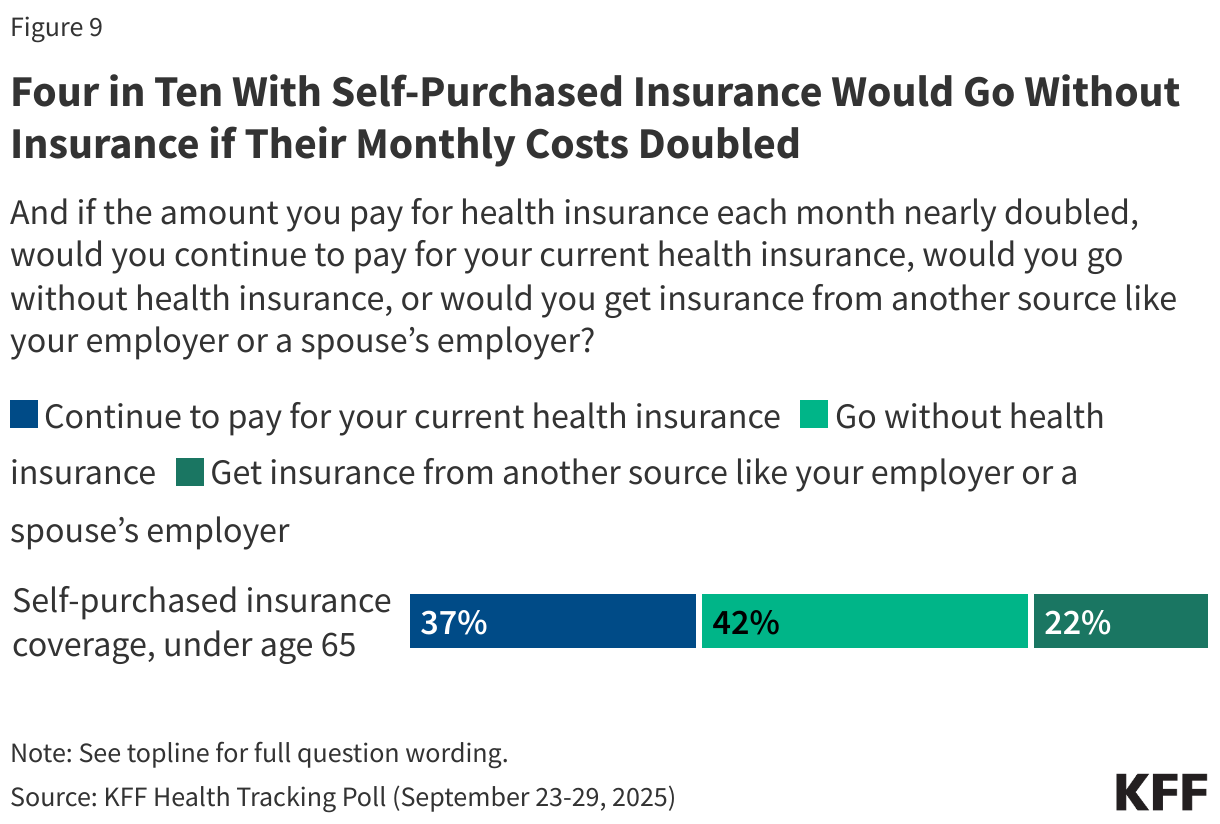
  • Seven in ten adults who buy their own health insurance say that if the amount they paid for health insurance each month nearly doubled, they could not pay the higher premiums without significantly disrupting their household finances. In addition, four in ten (42%) say they would go without health insurance coverage if the amount they had to pay for health insurance each month nearly doubled. About a third (37%) say they would continue to pay for their current health insurance, while two in ten (22%) would get insurance from another source, like an employer or a spouse’s employer.
  • Majorities across partisanship also report that they would be concerned if they heard about something of the outcomes for both letting the tax credits expire, as well as if Congress extended the tax cuts – granted to a lesser degree. Majorities say they would be concerned if they heard that health insurance would be unaffordable for many people who buy their own coverage (86%), that 4 million people would lose their health insurance coverage (86%), or if they heard that people who work at small businesses or are self-employed would be directly impacted (85%). On the other side, if Congress does extend these enhanced tax credits, two-thirds of the public (63%) say they would be concerned if they heard that it would require significant federal spending that would be largely paid for by taxpayers.
  • Three months after the passing of the tax and budget legislation, the bill still remains largely unfavorable among the public overall – lagging far behind both the Affordable Care Act and the ACA Marketplaces in overall popularity. Many are still unsure of how the legislation will impact them personally but four in ten (43%) think it’s most likely to hurt them and their families.

Public Still Largely Unaware That ACA Enhanced Tax Credits Are Expiring, Strong Support for Congress Extending Them

On October 1st the U.S. federal government shut down as Congress was unable to pass a stopgap spending bill. As part of the discussions around the federal budget, Democrats are seeking to include the extension of the enhanced premium tax credits (ePTCs) for people who purchase their own health insurance through the ACA Marketplace that are set to expire at the end of the year.

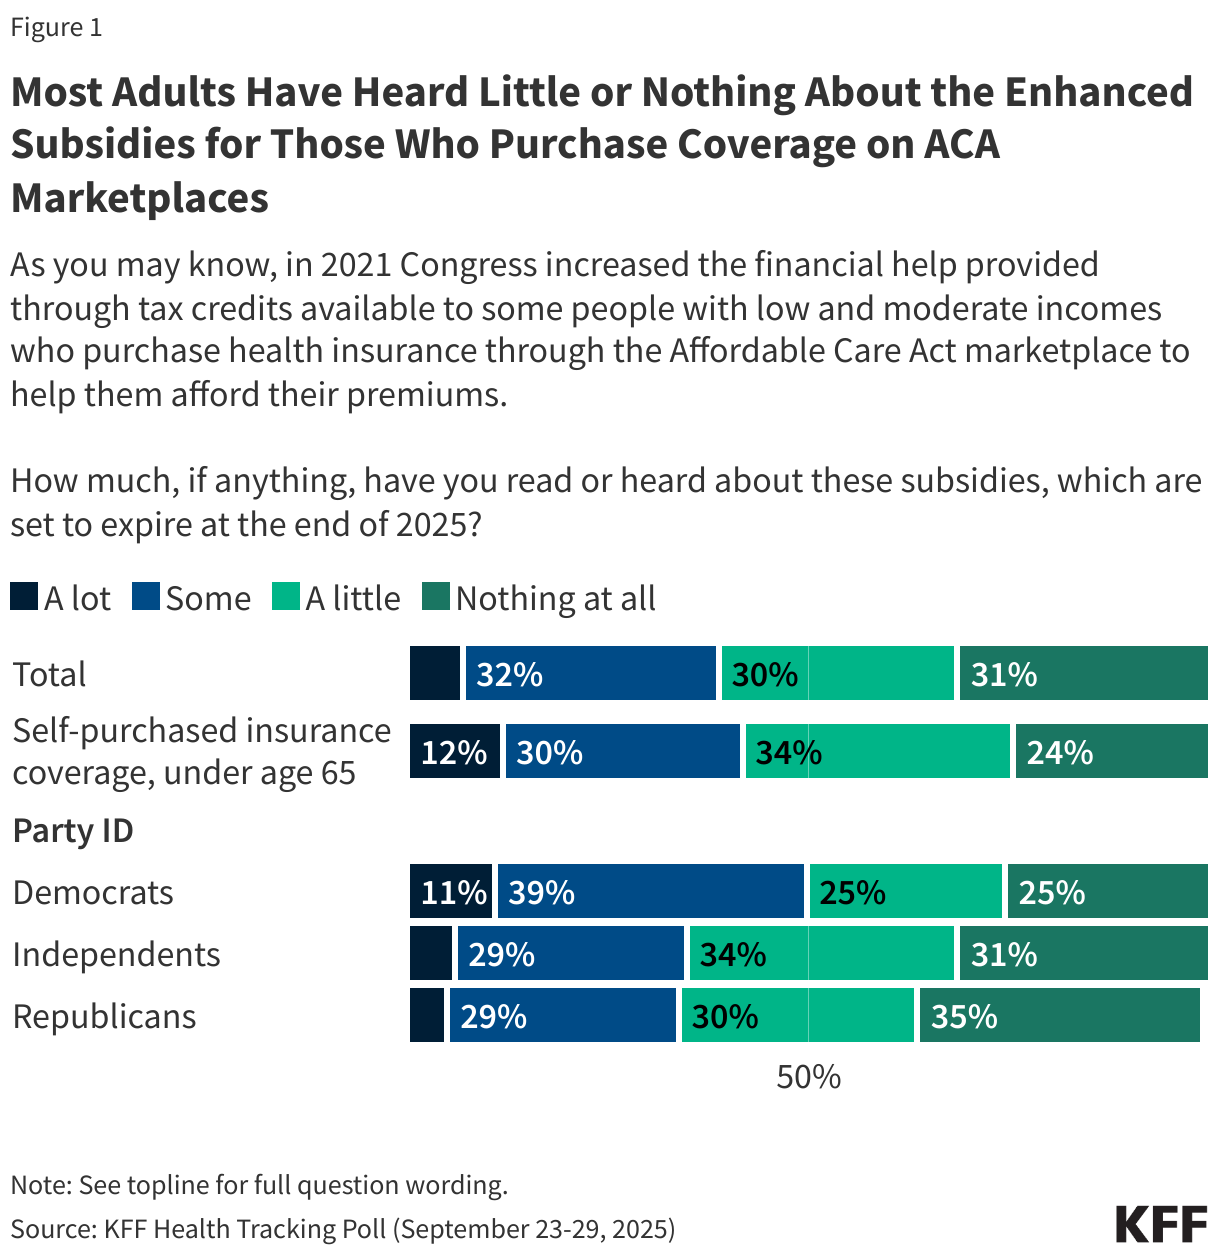
About six in ten adults say they have heard “a little” (30%) or “nothing at all” (31%) about the expiring ACA subsidies, showing widespread lack of information on the cost of coverage for over 24 million people in the U.S.  Four in ten say (39%) they’ve heard “a lot” or “some” – up from 27% in June of this year. Even among the group whose cost of coverage is expected to double next year – those who purchase their own insurance plans – about six in ten (58%) say they have heard just “a little” or “nothing at all” about the expiration of tax credits for people who self-purchased insurance.

Democrats seem to be more aware of the pending expiration, with about half of Democrats (50%) saying they have heard at least “some” about this, compared to about a third of independents (35%) and Republicans (34%).

Stacked bar chart showing the levels of public awareness about the enhanced ACA marketplace subsidies.

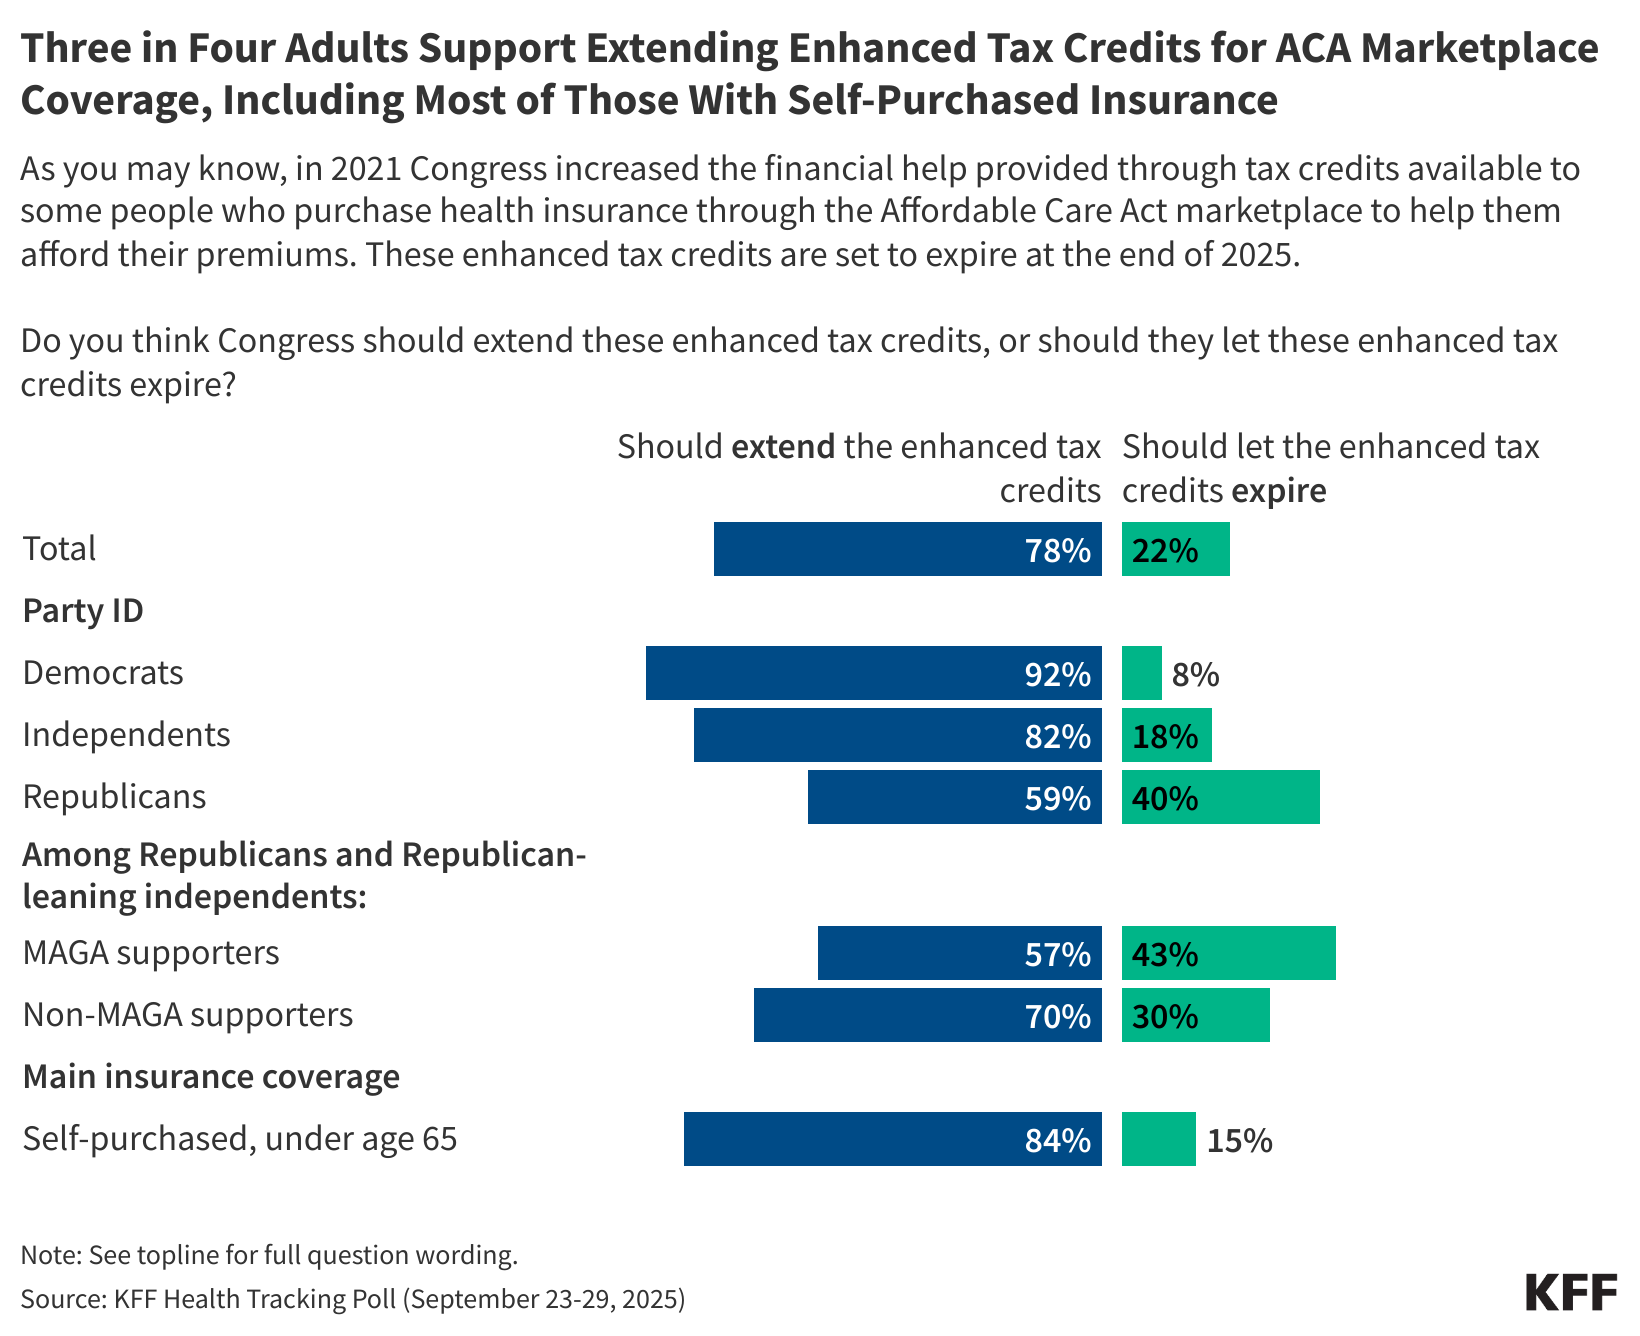
Once the public is told that the expiration date for subsidies is looming, about three-quarters (78%) of adults say Congress should extend the enhanced tax credits for people who buy their own insurance through the ACA Marketplace, more than three times the share (22%) who say Congress should let the credits expire. Over eight in ten (84%) of those who buy their own insurance say that Congress should extend the enhanced tax credits.

Although Republicans are more likely than Democrats and independents to say that Congress should let the credits expire, majorities across political party want Congress to extend the tax credits including nine in ten (92%) Democrats, eight in ten (82%) independents, and six in ten (59%) Republicans, including 57% of Republicans who align with the MAGA movement. 

Split bar chart showing the shares of adults who say the enhanced marketplace tax credits should be extended and those who say they should be allowed to expire.

Previous KFF polling has shown that attitudes towards the credits shift slightly after hearing counterarguments both for and against the extension of the credits. This month’s poll shows that large majorities of the public, including majorities of Democrats, independents, Republicans, and MAGA supporters are concerned about many of the potential consequences of letting these enhanced tax credits expire. Additionally, majorities of independents and Republicans and about half of Democrats are concerned about the consequences for extending them.

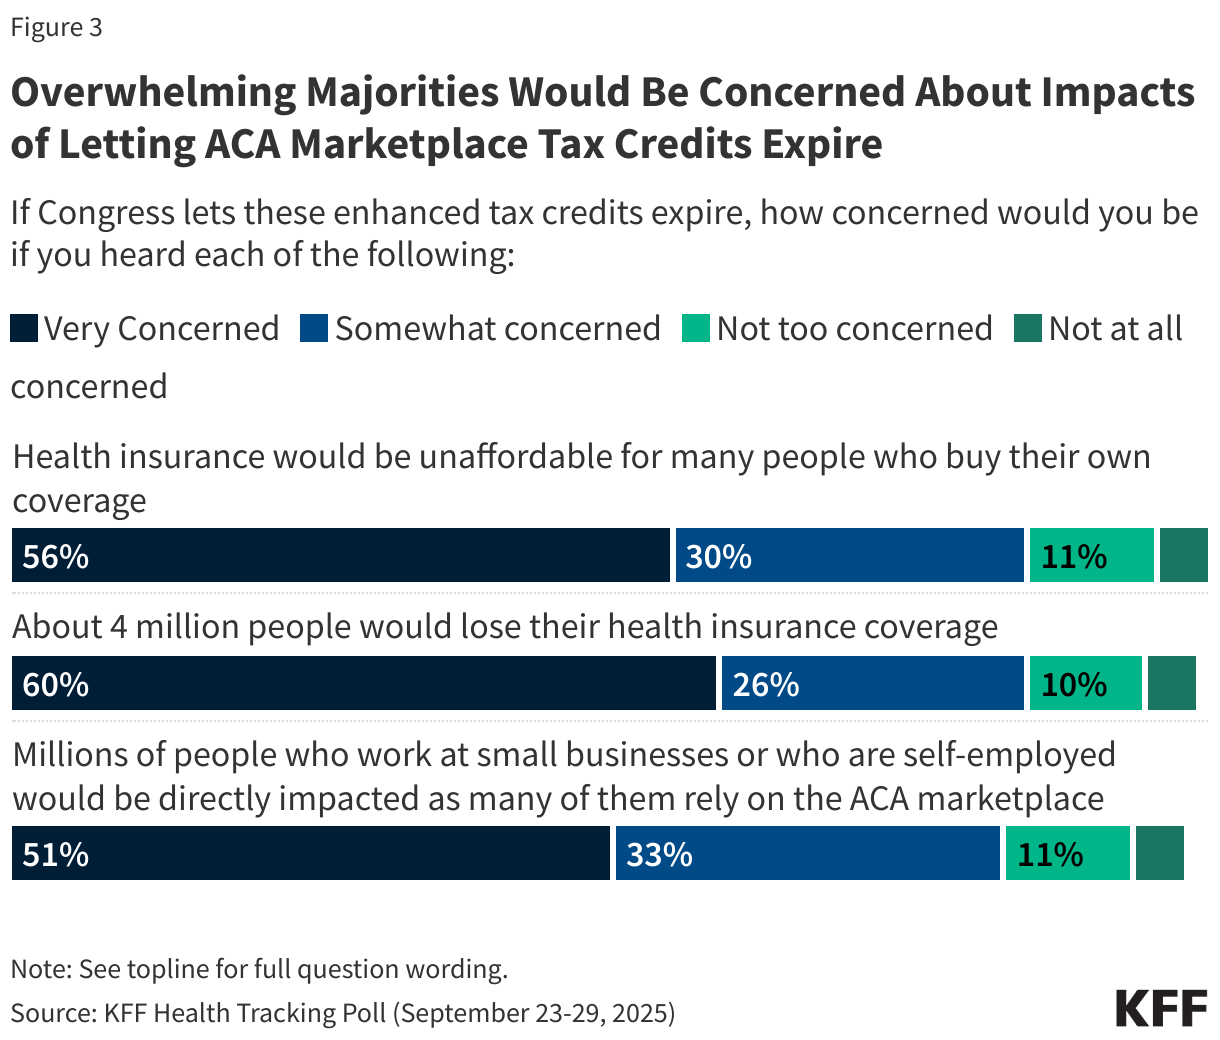
More than eight in ten adults say they would be concerned, including at least half who say they would be “very concerned,” if they heard that health insurance would be unaffordable for many people who buy their own coverage (86%), that 4 million people would lose their health insurance coverage (86%), or if they heard that people who work at small businesses or are self-employed would be directly impacted (85%).

Stacked bar charts showing the level of concern adults would have if they heard about impacts of letting the ACA marketplace tax credits expire.

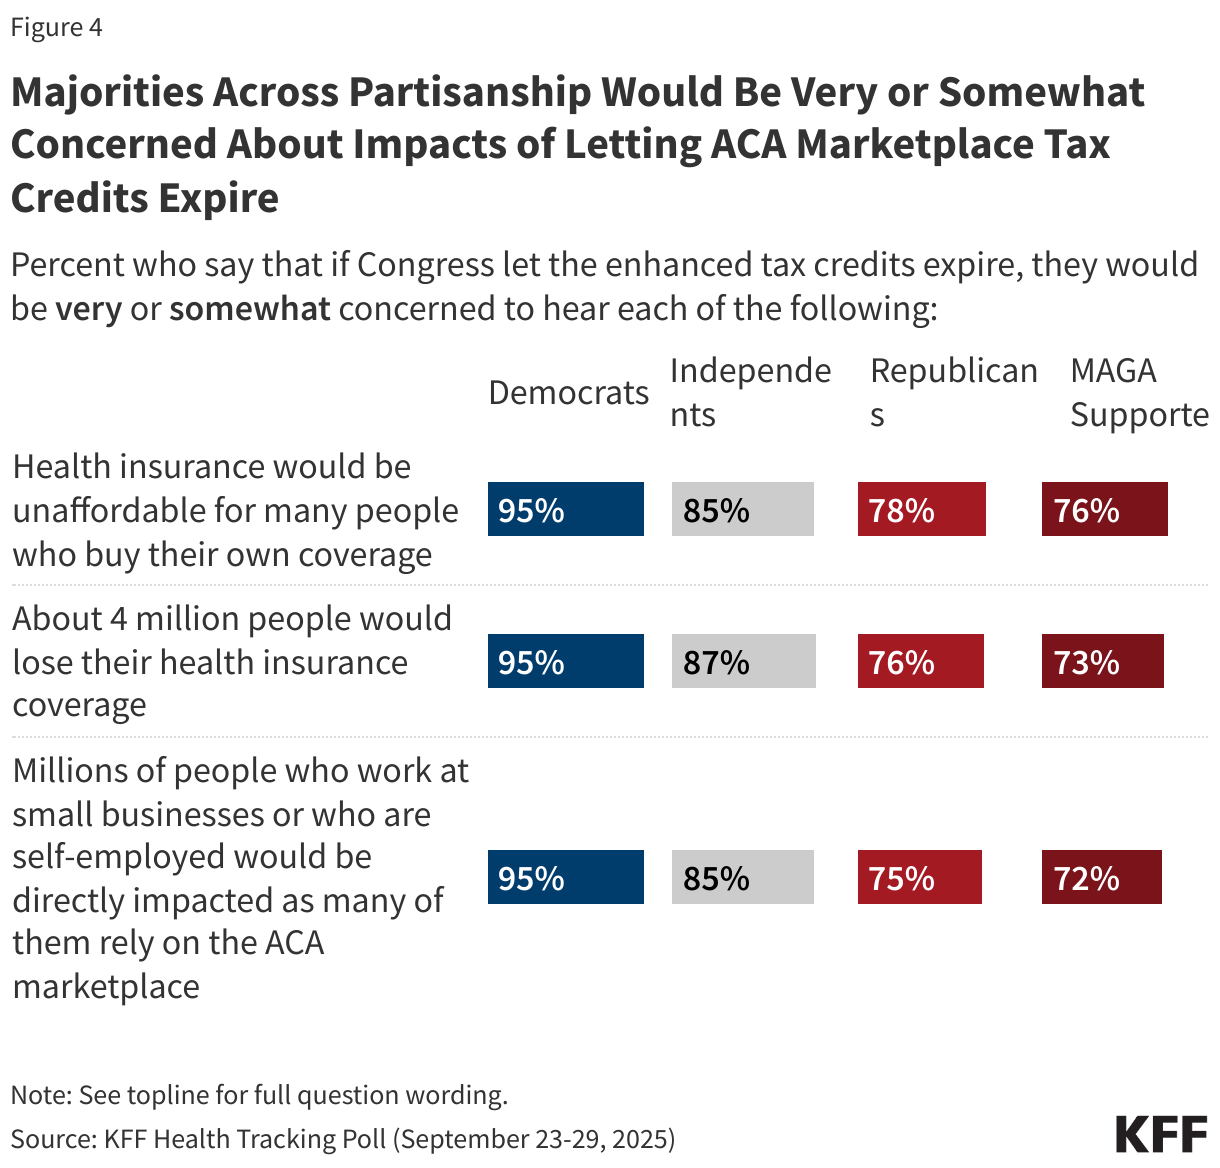
Concern over the possible consequences is high across party lines with large majorities of Democrats and independents saying they would be concerned about each of these potential outcomes, as well as three-quarters of Republicans and MAGA supporters.

Split bar chart showing shares by party who say they would be very or somewhat concerned to hear about impacts of letting ACA marketplace tax credits expire.

On the other side, if Congress does extend these enhanced tax credits, two-thirds (63%) of the public say they would be concerned if they heard that it would require significant federal spending that would be largely paid for by taxpayers, including a quarter (27%) who would be “very concerned.” This is predictably divided along partisan lines. More than eight in ten (83%) Republicans say they would be concerned about federal spending, but notably so do more than six in ten independents (61%) and nearly half of Democrats (49%). Republicans who support the MAGA movement are among the most worried about this issue, with almost half (47%) saying they would be “very concerned.”  
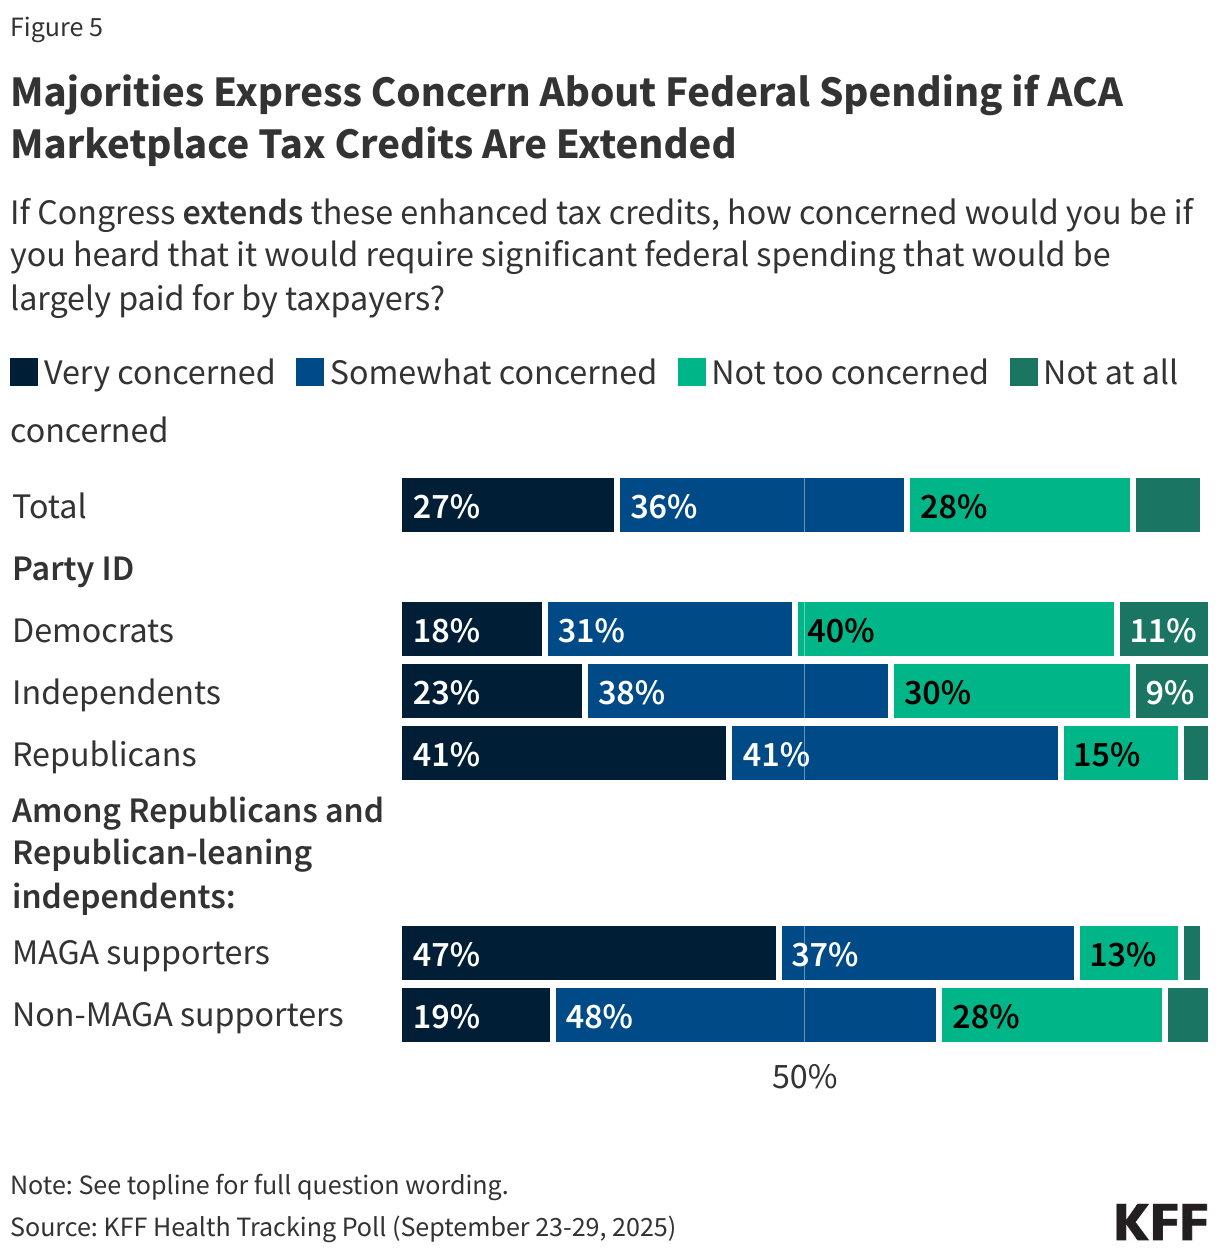
Stacked bar chart showing the levels of concern adults would have about federal spending if ACA marketplace tax credits were extended.

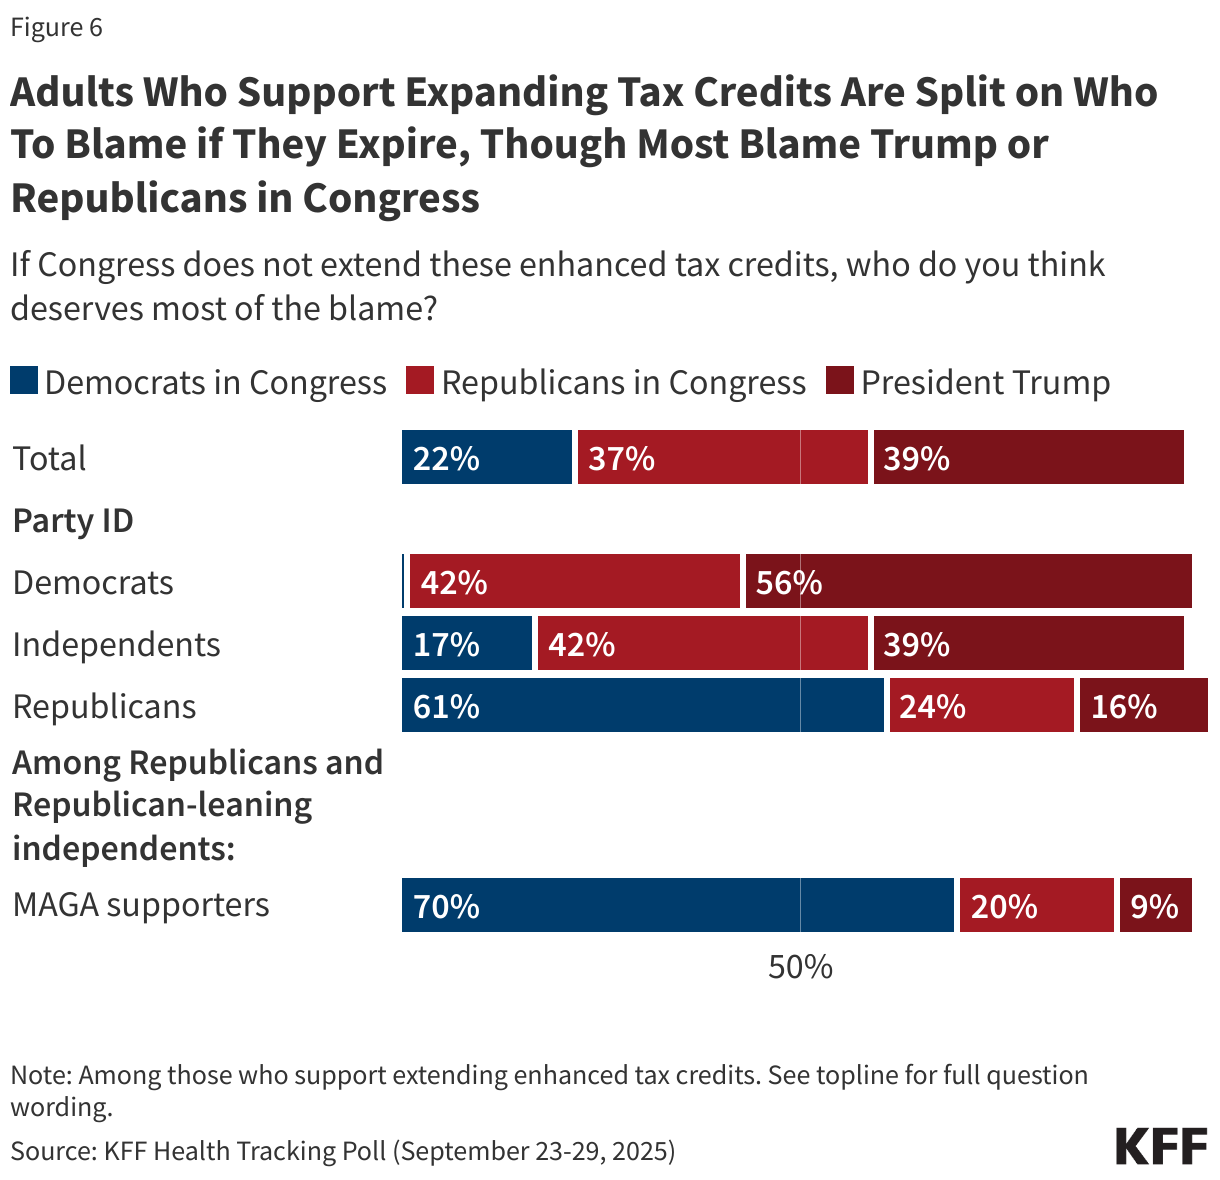
The poll finds more people say they would blame President Trump or Republicans in Congress than Democrats if tax credits are not extended. About four in ten (39%) adults who want to see the tax credits extended say that if Congress does not extend these enhanced tax credits, President Trump deserves most of the blame, while another four in ten (37%) say the same about Republicans in Congress. About two in ten (22%) say that Democrats in Congress deserve most of the blame, driven heavily by Republicans. Six in ten (61%) Republicans who want to see the tax credits extended say they would blame Democrats in Congress, including seven in ten MAGA Republicans, compared to one in six (17%) independents.

Over half of Democrats (56%) who want to see the tax credits extended say that if they are not extended, President Trump deserves most of the blame, though four in ten (42%) blame Republicans in Congress. Independents are largely split, with about four in ten saying they will blame Republicans in Congress (42%) or President Trump (39%).

Adults who purchased their own insurance, most of whom do so through the ACA Marketplace, are similarly split, with four in ten (42%) placing the blame if Congress does not extend the enhanced tax credits on Republicans in Congress and four in ten (37%) on President Trump. Two in ten (21%) of this group would blame Democrats in Congress if the subsidies expire. Notably, a previous KFF poll found that nearly half of adults enrolled in ACA Marketplace plans identify as Republican or lean Republican.

Stacked bar chart showing who the public would blame if Congress does not extend these enhanced tax credits.

Marketplace Enrollees Unsure How to Afford Coverage if Enhanced Tax Credits Expire

Six in ten adults who buy their own health insurance coverage think the cost of their personal health insurance would increase at least “some” if the tax credits are not extended, while about a quarter say they think it will increase “a little” (24%), or that their costs won’t increase at all (15%). Estimates are that the amount enrollees pay for premiums for ACA Marketplace plans will more than double on average and nearly 4 million people could eventually be uninsured. Notably, more than half of adults with Medicaid (54%) also say they think that if the enhanced tax credits expire the cost of their own coverage will also increase at least “some,” as do about four in ten people with Medicare age 65 and older and about half of people with employer-sponsored insurance.  It is important to note that the expiration of enhanced tax credits only directly impact people who buy their own coverage on the ACA Marketplace.
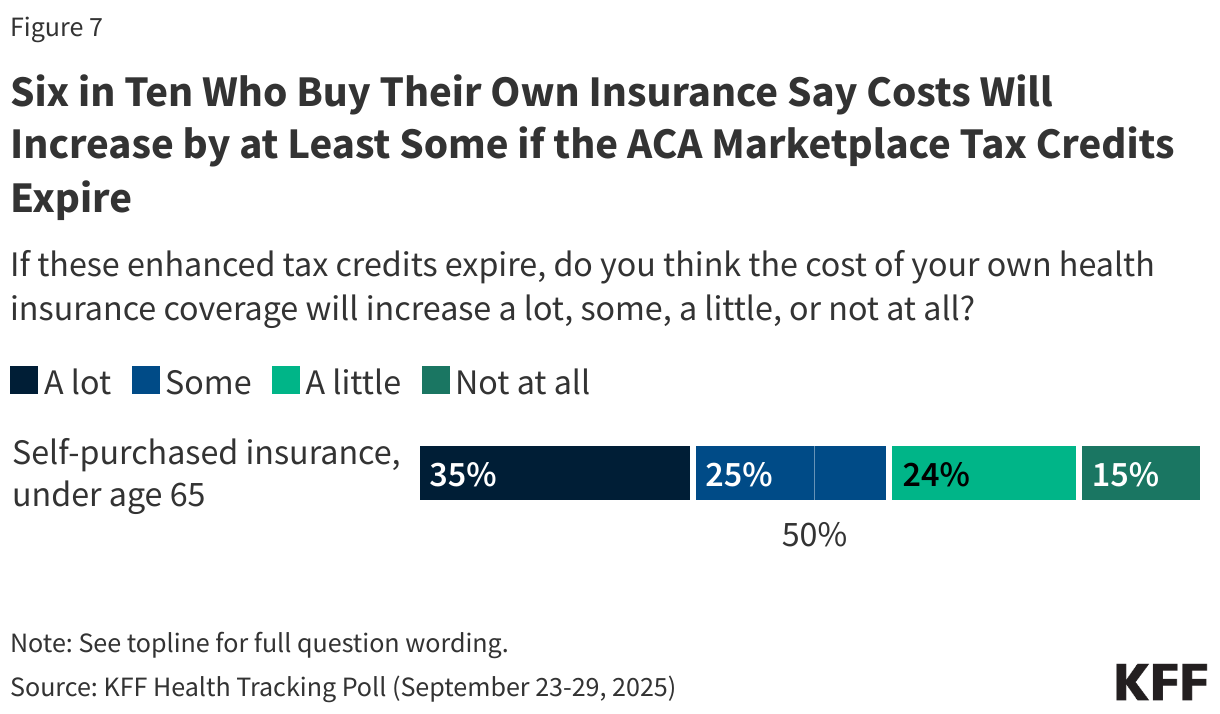
Stacked bar chart showing how much people who buy their own insurance think their health coverage will increase if the enhanced tax credits expire.

Among those who have insurance through the ACA Marketplace, seven in ten say that if the amount they paid for health insurance each month nearly doubled, they could not pay the higher premiums without significantly disrupting their household finances. Just three in ten estimate that they could pay the higher premiums.

Split bar chart showing the share of people with self-purchased insurance who say they would or would not be able to afford higher premiums if their coverage nearly doubled.

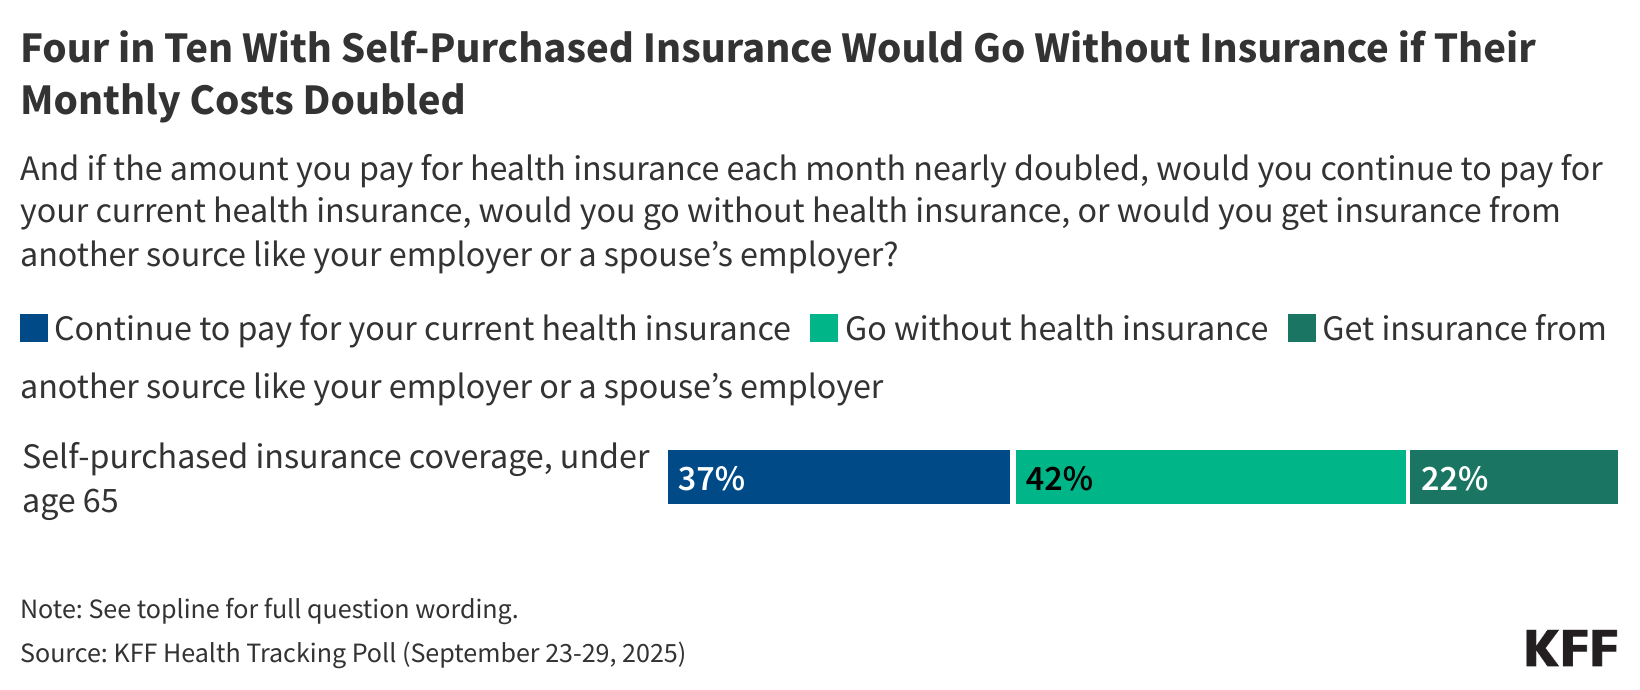
About four in ten (42%) Marketplace enrollees say they would go without health insurance coverage if the amount they had to pay for health insurance each month nearly doubled. Just over a third (37%) say they would continue to pay for their current health insurance, while about a quarter (22%) would get insurance from another source, like an employer or a spouse’s employer.

Stacked bar chart showing what the share of the public with self-purchased insurance would do if their health insurance nearly doubled.

Public Views of Major Health Care Legislation

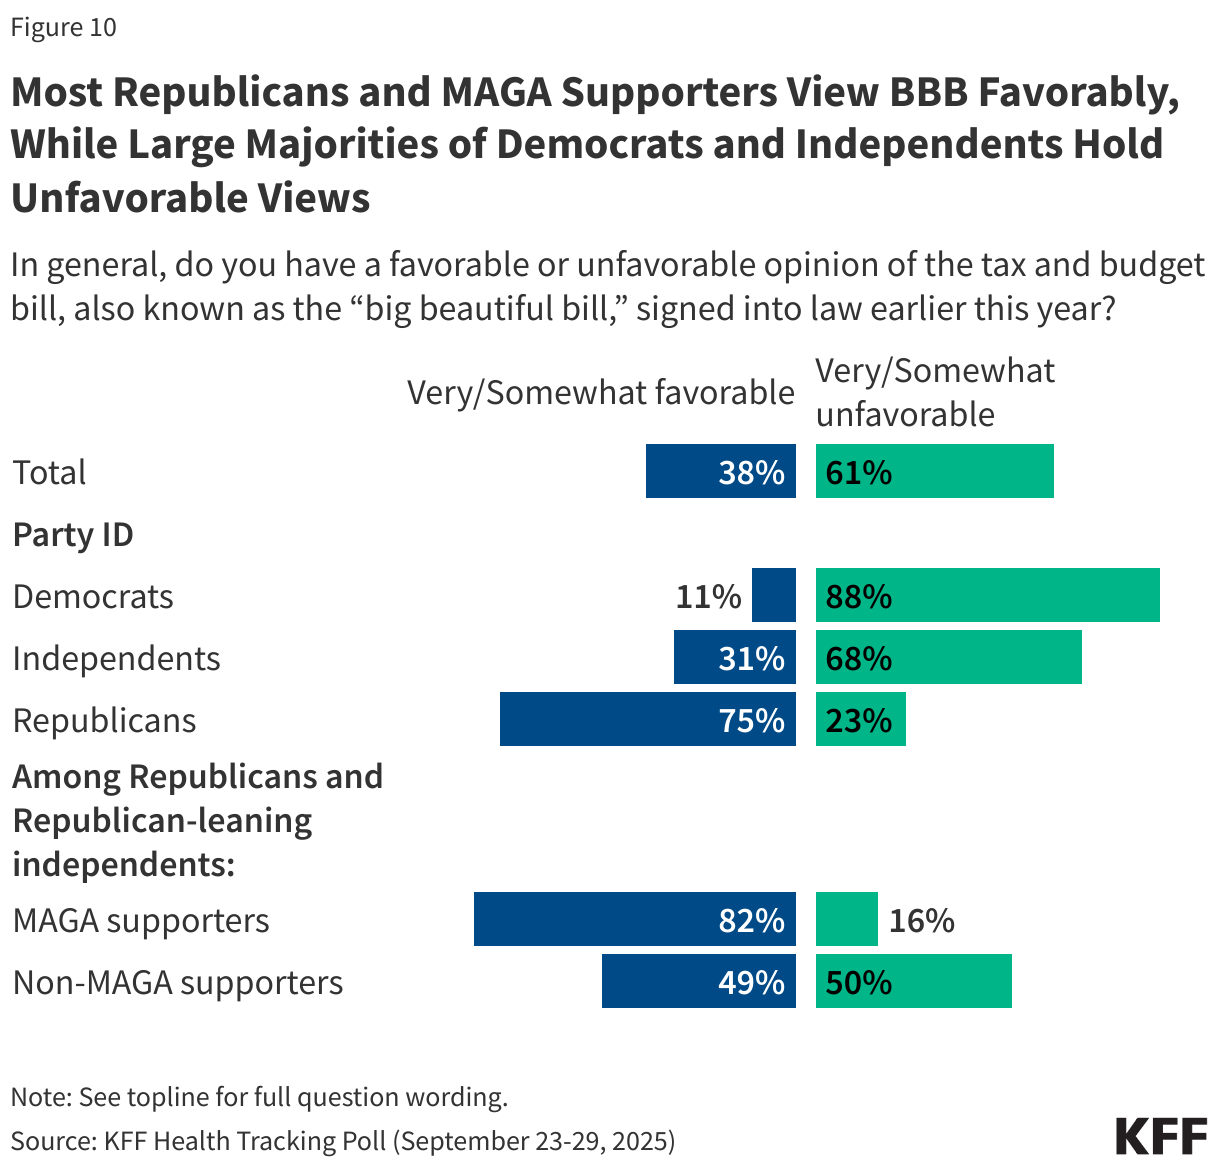
On July 4, 2025, President Trump signed a sweeping legislative package known as the “Big Beautiful Bill,” that included significant changes to the country’s Medicaid program and the Affordable Care Act (ACA) Marketplaces. The package, which passed on a party-line vote, with no Democrats in favor, has been described as the biggest rollback of the country’s health care programs in modern history. Now, as part of federal budget negotiations, Democrats in Congress, are seeking to minimize some of these health insurance rollbacks. The latest KFF Health Tracking Poll shows both parties are playing to their bases, with Republicans strongly supporting the “Big Beautiful Bill” (BBB) legislation and Democrats largely opposed.

Overall, about four in ten (38%) adults hold favorable views of the tax and budget legislation passed earlier this year, including three-quarters of Republicans (75%) and eight in ten (82%) Republicans or Republican-leaning independents who support the MAGA movement. Democrats and independents, on the other hand, largely hold unfavorable views of the legislation, including nearly nine in ten (88%) Democrats and two-thirds (68%) of independents who say they view the law unfavorably.

Split bar chart showing the share of the public who have a favorable or unfavorable view of the "big beautiful bill".

The share of the public who say they have a favorable opinion of the tax and budget legislation has stayed relatively stable, at close to four in ten (38%), similar to 36% in July and 35% in June.

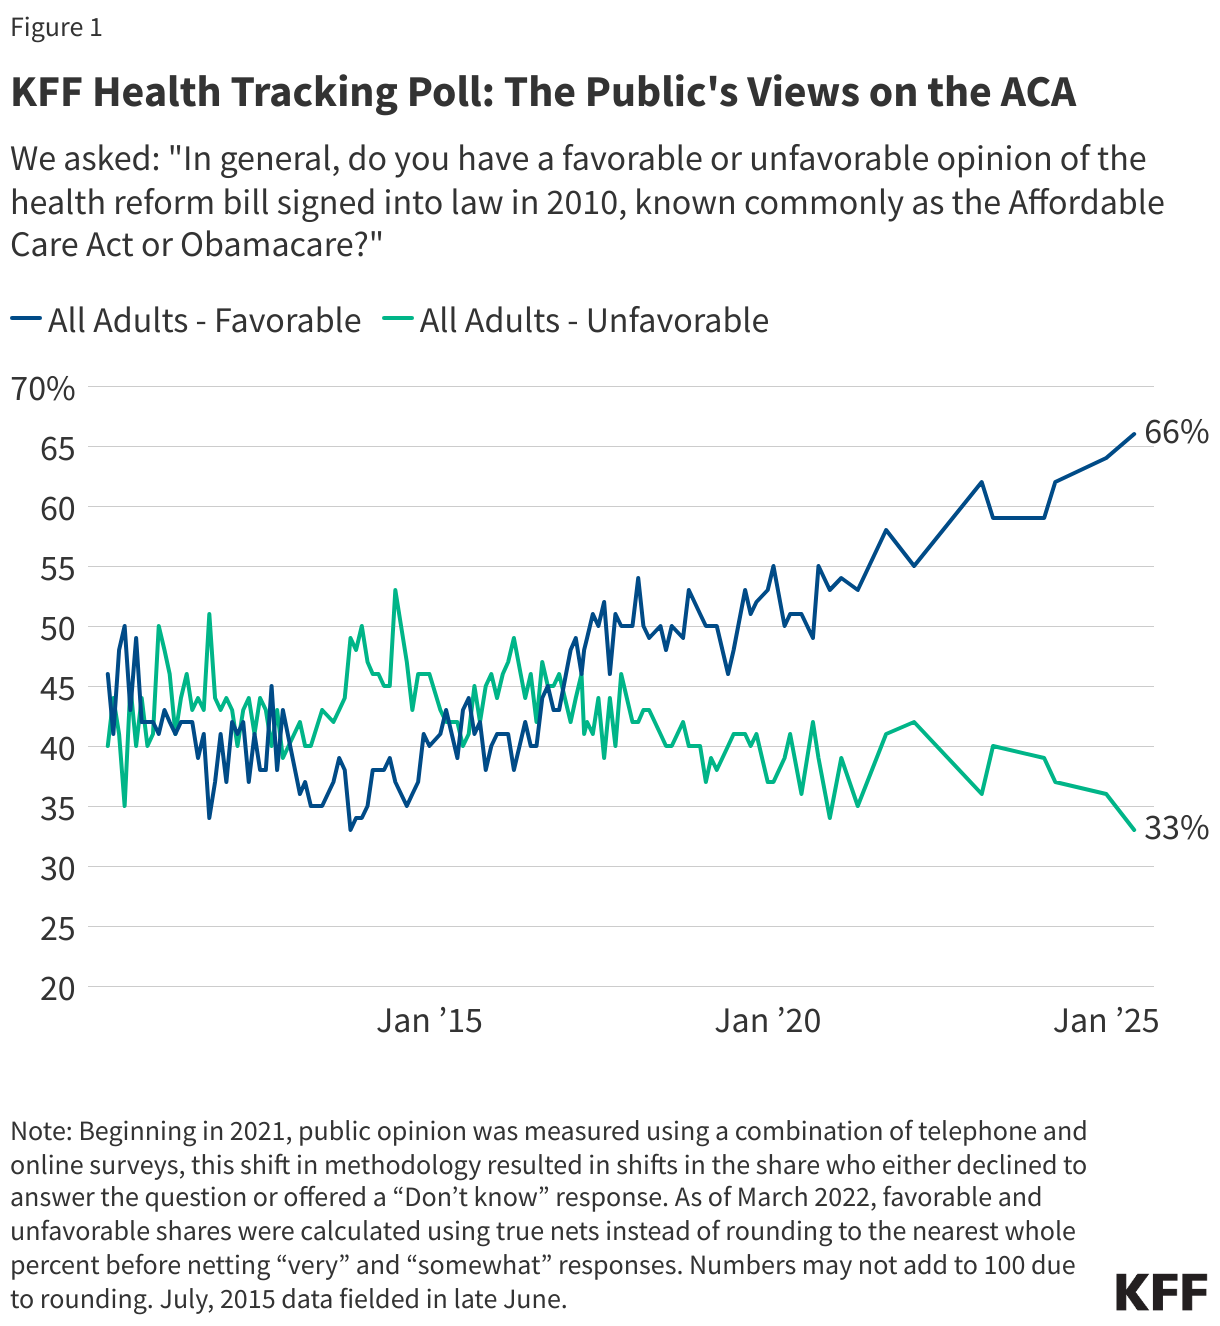
Overall favorability of the 2010 health care law known as the Affordable Care Act (ACA) continues to be at historically high levels, with about two-thirds (64%) of the public viewing the law positively. This is largely driven by Democrats and independents, with over nine in ten (94%) Democrats and two-thirds (64%) of independents viewing the law favorably, while two-thirds (64%) of Republicans have an unfavorable view. Click here to explore more than ten years of polling on the ACA.

Majorities Across Partisans View ACA Marketplaces Favorably

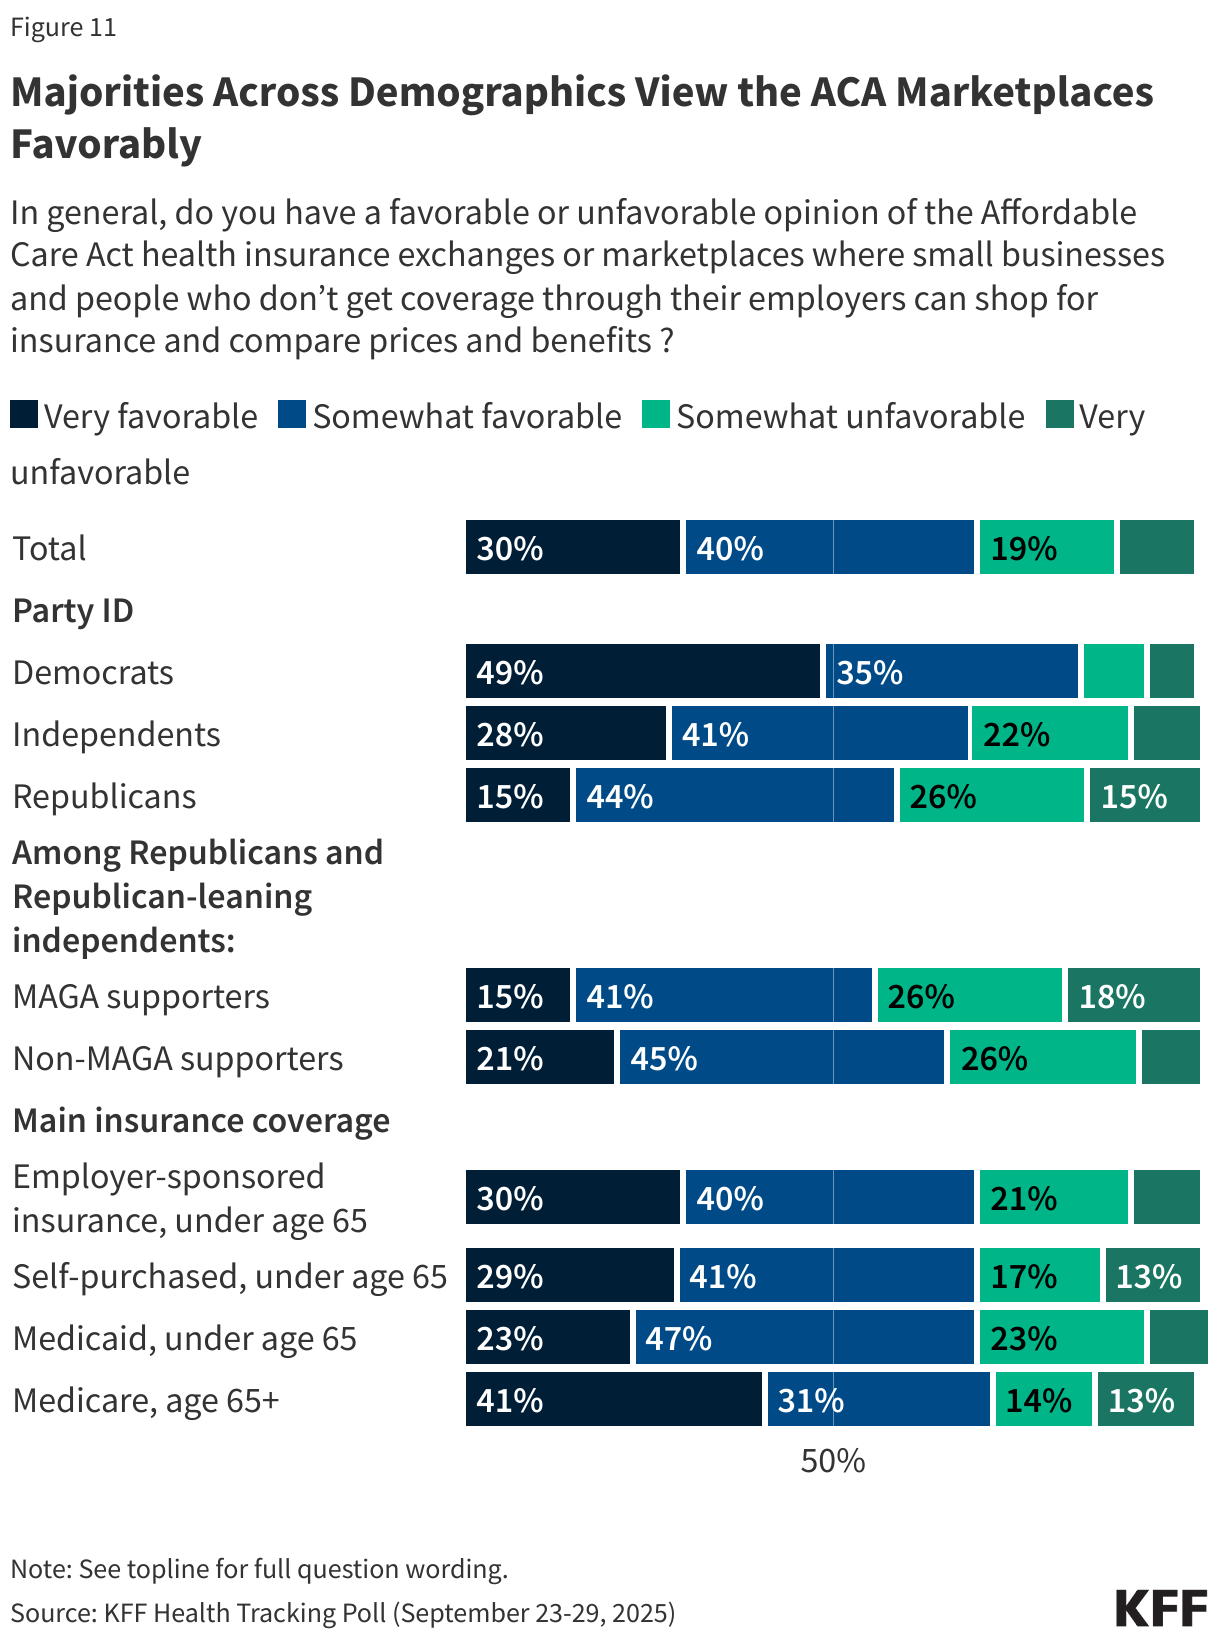
The ACA Marketplaces where people and small businesses can shop for health insurance are even more popular than the ACA itself, with seven in ten (70%) adults having a favorable view. The ACA Marketplaces have consistently been a more popular provision of the ACA, even before Congress passed the American Rescue Plan Act (ARPA) in 2021, which provided temporarily enhanced tax credits to adults who purchased their own health insurance through the Marketplaces. Though views of the ACA Marketplace are divided by partisanship, majorities across party lines view the ACA Marketplace positively, with eight in ten (84%) Democrats, seven in ten (69%) independents, and six in ten (59%) Republicans holding a favorable view. This also includes MAGA Republicans and Republican-leaning independents, among whom over half (56%) hold a favorable opinion of the Marketplace.

Among those who purchase their health care plan themselves, many of whom bought through the ACA Marketplace, seven in ten have a favorable opinion of the ACA health insurance exchanges or Marketplaces.

Stacked bar chart showing the public's level of favorability toward the ACA marketplaces.

Many Still Unsure How the “Big Beautiful Bill” Will Impact Them

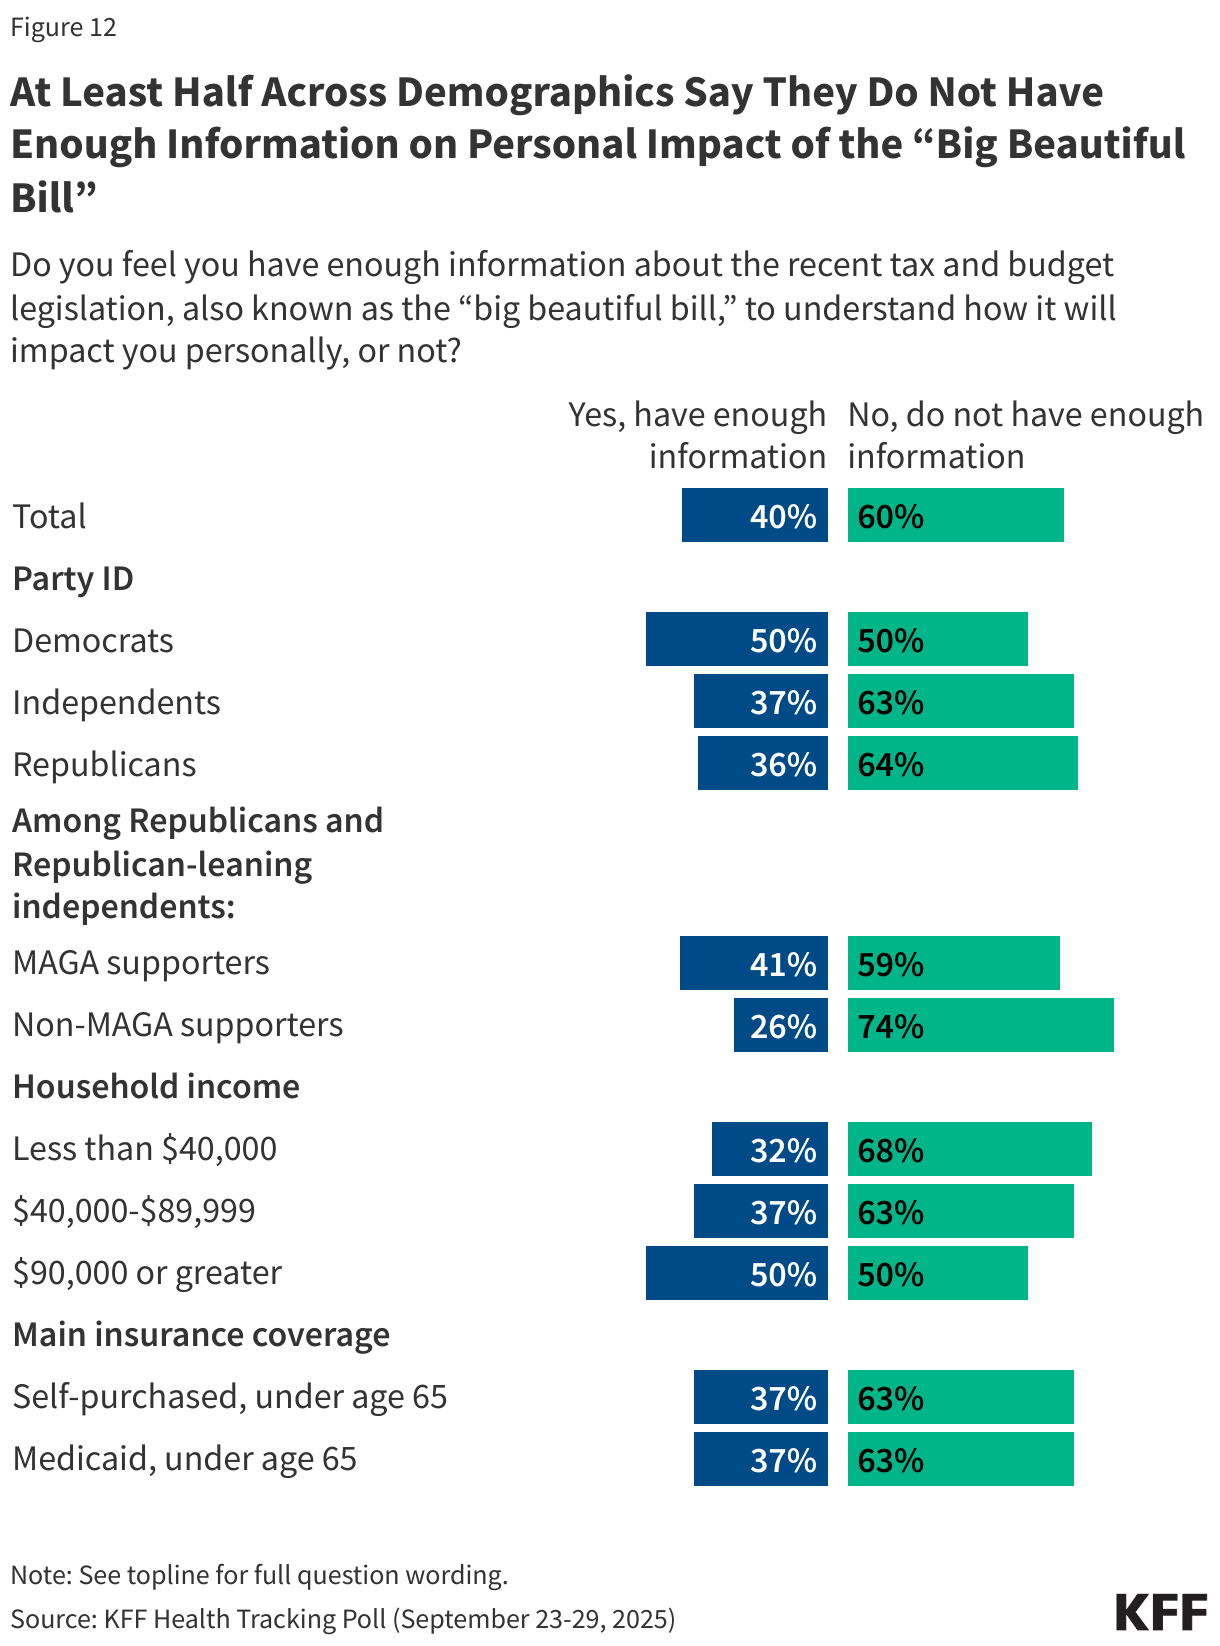
Three months after the passing of President Trump’s major legislative achievement, the “Big Beautiful Bill,” most people remain unaware of how the effects of the tax and budget legislation will impact them. Six in ten adults say they do not have enough information as to how the legislation will impact them personally, while four in ten report that they do have enough information.

Democrats (50%) are more likely than Republicans (36%) and independents (37%) to say they have enough information about how the BBB will impact them personally. About four in ten (41%) Republicans and Republican-leaning independents who identify with the MAGA movement say they have enough information about the impact of the legislation, though majorities (59%) still do not.

The BBB legislation has made changes to the ACA Marketplaces including limiting some eligibility and shortening the open enrollment period. Among those who purchase their own health insurance, two-thirds (63%) say they do not have enough information about how the legislation will impact them. 

Split bar chart showing the share of adults who say they either have enough information or not enough information about the "big beautiful bill".

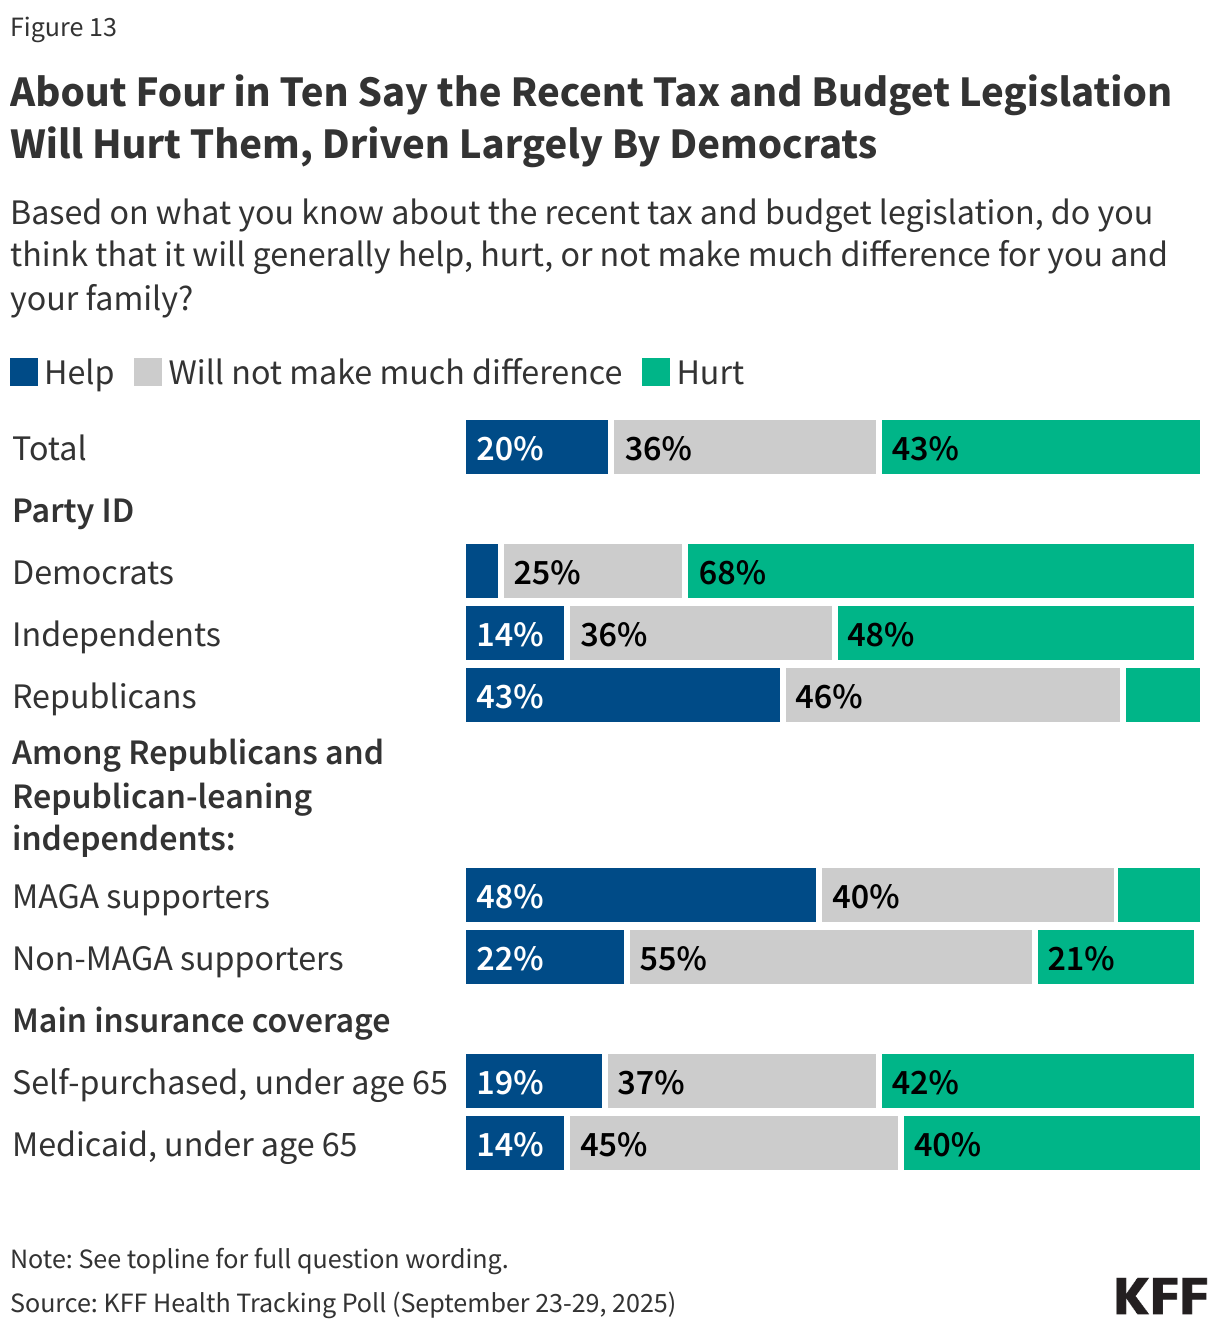
While many say they don’t have enough information about how the tax and budget legislation will affect them, partisanship once again plays a major role in public perception of the law’s impact. About four in ten (43%) say the recent legislation will generally hurt them and their families, which is twice the share who say the legislation will generally help them. More than a third of the public (36%) say the law won’t make a difference to them and their families.

Two-thirds (68%) of Democrats say the tax and budget legislation will generally hurt them and their families, as do about half (48%) of independents. Republicans are split between thinking the law will help them and thinking it won’t make a difference, with similar shares saying the law will help them and their families (43%) and saying they don’t think the law will make a difference for them (46%). Nearly half of Republicans and leaners who support the MAGA movement say the law will help them (48%) while four in ten say it won’t make a difference for them. Very few MAGA supporters (11%) say the law will hurt them.

Among those who purchase their own insurance, many through the ACA Marketplace, four in ten (42%) expect the legislation will generally hurt them and their family, while similar share (37%) expects it to not make much of a difference and just one in five (19%) say it will help.

Stacked bar chart showing the share of the public's views on how the big beautiful bill will impact them and their family.

This KFF Health Tracking Poll was designed and analyzed by public opinion researchers at KFF. The survey was conducted September 23-29, 2025, online and by telephone among a nationally representative sample of 1,334 U.S. adults in English (n=1,255) and in Spanish (n=79). The sample includes 1,026 adults (n=64 in Spanish) reached through the SSRS Opinion Panel either online (n=1,004) or over the phone (n=22). The SSRS Opinion Panel is a nationally representative probability-based panel where panel members are recruited randomly in one of two ways: (a) Through invitations mailed to respondents randomly sampled from an Address-Based Sample (ABS) provided by Marketing Systems Groups (MSG) through the U.S. Postal Service’s Computerized Delivery Sequence (CDS); (b) from a dual-frame random digit dial (RDD) sample provided by MSG. For the online panel component, invitations were sent to panel members by email followed by up to three reminder emails. 

Another 308 (n=15  in Spanish) adults were reached through random digit dial telephone sample of prepaid cell phone numbers obtained through MSG. Phone numbers used for the prepaid cell phone component were randomly generated from a cell phone sampling frame with disproportionate stratification aimed at reaching Hispanic and non-Hispanic Black respondents. Stratification was based on incidence of the race/ethnicity groups within each frame. Among this prepaid cell phone component, 141 were interviewed by phone and 167 were invited to the web survey via short message service (SMS). 

Respondents in the prepaid cell phone sample who were interviewed by phone received a $15 incentive via a check received by mail. Respondents in the prepaid cell phone sample reached via SMS received a $10 electronic gift card incentive. SSRS Opinion Panel respondents received a $5 electronic gift card incentive (some harder-to-reach groups received a $10 electronic gift card). In order to ensure data quality, cases were removed if they failed two or more quality checks: (1) attention check questions in the online version of the questionnaire, (2) had over 30% item non-response, or (3) had a length less than one quarter of the mean length by mode. Based on this criterion, no cases were removed.

The combined cell phone and panel samples were weighted to match the sample’s demographics to the national U.S. adult population using data from the Census Bureau’s 2024 Current Population Survey (CPS), September 2023 Volunteering and Civic Life Supplement data from the CPS, and the 2025 KFF Benchmarking Survey with ABS and prepaid cell phone samples. The demographic variables included in weighting for the general population sample are gender, age, education, race/ethnicity, region, civic engagement, frequency of internet use, and political party identification. The weights account for differences in the probability of selection for each sample type (prepaid cell phone and panel). This includes adjustment for the sample design and geographic stratification of the cell phone sample, within household probability of selection, and the design of the panel-recruitment procedure.

The margin of sampling error including the design effect for the full sample is plus or minus 3 percentage points. Numbers of respondents and margins of sampling error for key subgroups are shown in the table below. For results based on other subgroups, the margin of sampling error may be higher. Sample sizes and margins of sampling error for other subgroups are available on request. Sampling error is only one of many potential sources of error and there may be other unmeasured error in this or any other public opinion poll. KFF public opinion and survey research is a charter member of the Transparency Initiative of the American Association for Public Opinion Research. 

GroupN (unweighted)M.O.S.E.
Total1,334± 3 percentage points
Party ID
Democrats418± 6 percentage points
Independents455± 6 percentage points
Republicans385± 6 percentage points
MAGA Republicans374± 6 percentage points


News Release

Despite Budget Concerns, Three-Quarters of Public Say Congress Should Extend the Enhanced ACA Tax Credits Set to Expire Next Year, Including Most Republicans and MAGA Supporters

7 in 10 Marketplace Enrollees Say They Could Not Afford Coverage if Their Premiums Doubled; 4 in 10 Say They Would Expect to Be Uninsured

Published: Oct 3, 2025

More than three-quarters (78%) of the public say they want Congress to extend the enhanced tax credits available to people with low and moderate incomes to make the health coverage purchased through the Affordable Care Act’s Marketplace more affordable, a new KFF Health Tracking Poll finds. That’s more than three times the share (22%) who say they want Congress to let the tax credits expire.

Most Republicans (59%) and “Make American Great Again” supporters (57%) favor extending the enhanced tax credits, which otherwise would expire at the end of the year and require Marketplace customers to pay much more in premiums to retain coverage. Larger majorities of Democrats (92%) and independents (82%) also support extending the enhanced tax credits, as do most people who buy their own health insurance, most of whom purchase through the Marketplace (84%).

The poll also tests the public’s response to arguments made by those who support and oppose extending the enhanced tax credits.

Among the public overall, more than eight in 10 say they would be concerned about the expirations of the tax credits if they heard that health insurance would become unaffordable for many people who buy their own coverage (86%), that about 4 million people would lose their health insurance coverage (86%), or that millions of people who work at small businesses or are self-employed would be directly impacted because they rely on the ACA Marketplace (85%).

In the other direction, a smaller majority (63%) say they would be concerned about extending the enhanced tax credits if they heard that it would require significant federal spending that would largely be paid by taxpayers. This includes a large majority of Republicans (83%) and most independents (61%).

When people who want to extend the enhanced tax credits were asked who deserves the most blame if they expire, roughly equal shares say President Trump (39%) and Republicans in Congress (37%), while a smaller share (22%) say that Democrats in Congress would deserve most of the blame.

“There is a hot debate in Washington about the looming ACA premium hikes, but our poll shows that most people in the marketplaces don’t know about them yet and are in for a shock when they learn about them in November,” KFF President and CEO Drew Altman said.

The poll was fielded just prior to the Oct. 1 federal government shutdown that was triggered in part by disagreements about whether, how and when to extend the expiring tax credits. A recent KFF analysis finds that losing that extra help would increase what Marketplace enrollees receiving financial assistance pay in premiums by an average of 114% – from $888 in 2025 to $1,904 next year.

The poll suggests that many Marketplace enrollees are going to be surprised by the jump in their premiums if the tax credits aren’t renewed in time for 2026 open enrollment period, which starts Nov. 1.

Among people who buy their own coverage (largely through the Marketplaces), about six in ten (58%) say they have heard just “a little” or “nothing at all” about the expiration of tax credits for eligible people with Marketplace coverage.

Among those who buy their own insurance, about a third (35%) expect their premiums to increase “a lot” next year.  A quarter (25%) expect their premiums to rise “some,” another quarter (24%) expect their premiums to increase “a little,” and the rest (15%) don’t expect any increase.

When asked if they could afford health coverage if their premiums nearly doubled, seven in 10 (70%) of those who purchase their own insurance say they would not be able to afford the premiums without significantly disrupting their household finances, more than twice the share (30%) who say they could afford the higher premiums.

About four in 10 (42%) Marketplace enrollees say they would go without health insurance coverage if the amount they had to pay for health insurance each month nearly doubled. Similar shares (37%) say they would continue to pay for their current health insurance, while two in 10 (22%) say they would get insurance from another source, like an employer or a spouse’s employer.

Other findings include:

  • Nearly two thirds (64%) of the public continue to hold favorable views of the Affordable Care Act overall, and a somewhat larger majority (70%) holds favorable views of the ACA’s Marketplaces. While two thirds (64%) of Republicans view the overall ACA unfavorably, most (59%) view the ACA Marketplaces themselves favorably.
  • Most (61%) of the public holds unfavorable views of the tax and budget law enacted in July, also known as the “big beautiful bill,” while about four in 10 (38%) view it favorably. Large majorities of Democrats (88%) and independents (68%) view the law unfavorably, while similar majorities of Republicans (75%) and MAGA supporters (82%) view it favorably.

Designed and analyzed by public opinion researchers at KFF, this survey was conducted September 23-29, 2025, online and by telephone among a nationally representative sample of 1,334 U.S. adults in English and in Spanish. The margin of sampling error is plus or minus 3 percentage points for the full sample. For results based on other subgroups, the margin of sampling error may be higher.

Health Policy Issues in Women’s Health

Table of Contents

Introduction

Copy link to Introduction

Health care is a central element of women’s lives, shaping their ability to care for themselves and their families, to be productive members of their communities, to contribute to the workforce, and to build a base of economic security. Women’s reproductive health care needs, their central roles managing family health as parents and as family caregivers, and their longer lifespans, albeit with greater rates of chronic health problems and functional limitations than men, all shape their relationships with the health care system. While women are major consumers of health care services and play a central role as health navigators and caregivers for their families, structural factors can challenge their ability to get the health care they need. Factors, including national and state policies that shape the health care delivery system to research priorities and discriminatory economic and societal forces, can deprioritize women’s health concerns. Access challenges are greater for women who are in low-income households, who face structural and societal racism and discrimination, who struggle with complex or understudied medical conditions, or who live in states or communities that have enacted or invested in policies and programs that do not support their health needs.

In the United States, the women’s health movement gained significant traction in the 1960s and 1970s as part of a larger grassroots women’s rights movement that challenged long-standing inequities and discrimination that limited women’s economic and social opportunities. The book, “Our Bodies, Ourselves,” brought a wide range of women’s health concerns, ranging from abortion and sexuality to menopause and cancer, into the mainstream. Over time, federal action also began to address many of the long-standing discriminatory sex and gender-based policies that were baked into our employment, health, and research policies. The 1973 U.S. Supreme Court ruling in Roe v. Wade decriminalized and protected the right to abortion care for nearly 50 years; the Pregnancy Discrimination Act of 1978 offered workplace and insurance protections to pregnant workers; the National Institutes of Health (NIH) Revitalization Act of 1993 mandated the inclusion of women in clinical research and formally established the NIH Office of Women’s Health; and in 2010, the Affordable Care Act (ACA) banned many of the discriminatory practices that had shaped women’s coverage of and access to care. While many of these policy changes have resulted in improvements and advances in women’s health, including access and coverage, the advances have not been linear.  In 2022, the Supreme Court, with a conservative supermajority, struck down the right to abortion in Dobbs v Jackson Women’s Health, resulting in the outright banning of abortion in many states. Despite advances in women’s health research, many gaps remain and the Trump Administration has targeted and blocked federal funding that focuses on gender, a pillar of women’s health research.     

This primer focuses on some of the key areas disproportionately affecting women today that are shaped by national and state health policies. This includes health coverage and costs, reproductive health services, maternal health, mental health, and intimate partner violence. In addition, it highlights some of the structural factors and inequities that still impact women’s health, particularly women of color and gender-expansive individuals such as those who are transgender or non-binary or otherwise gender fluid or non-conforming who are at risk of being marginalized or discriminated against by their health coverage or providers. We note that while we refer to “women” and “women’s health” throughout this chapter, some persons assigned female sex at birth do not identify as women, such as transgender men, non-binary individuals, and otherwise gender-expansive individuals. Still, many of the issues discussed in this chapter also apply to them.

What Is the Demographic Profile of Women?

Copy link to What Is the Demographic Profile of Women?

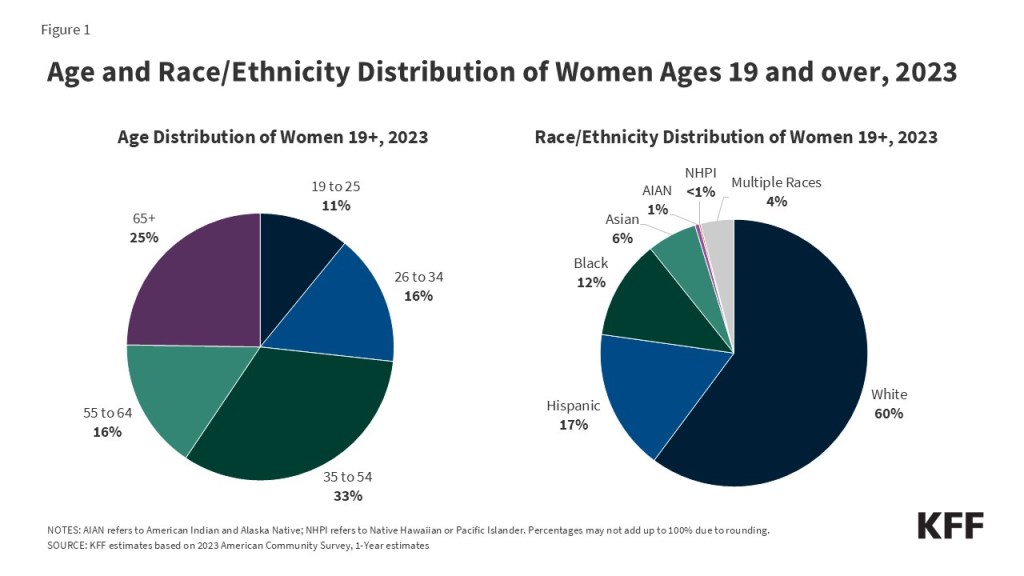
More than 128 million adult women over the age of 19 live in the U.S. today, with great diversity in many demographic characteristics. A third of adult women are between the ages of 35-54 (33%) and the majority are White (60%) (Figure 1). Nearly 1 in 5 (17%) women are Hispanic, 12% are Black and 6% are Asian.

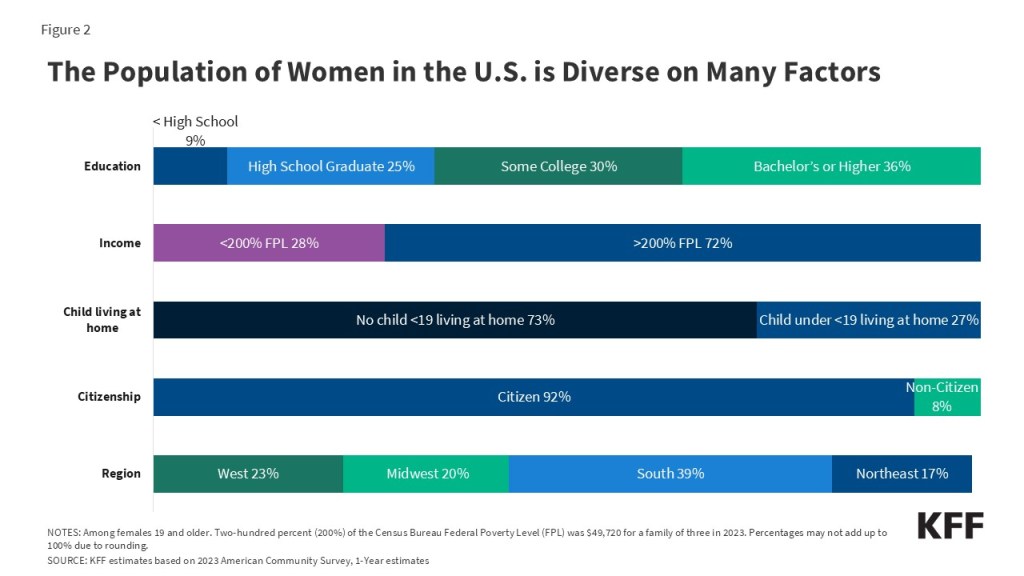
Almost two-thirds (65%) of women live in a household with at least one full-time worker, while 1 in 10 (9%) live in a household with only part-time workers, and 25% of women live in households with no workers (data not shown). Given the important role of employment in shaping health coverage, workforce participation is a significant determinant of the type of health insurance that working women or women who live in households with full-time workers can obtain.

While most women in the U.S. report having good health, nearly 1 in 5 (18%) women 18 and older rate their health as “fair” or “poor” and 14% report having a disability such as difficulty with vision, hearing, or walking. As women age, they are more likely to experience chronic health problems and declines in health status. These factors are highly predictive of their need for and use of health care services.

Income also plays a major role in health coverage and access to care. Income affects the resources that women have to pay for out-of-pocket health care costs and contribute to premium costs. Income also determines women’s eligibility for programs such as Medicaid or subsidies to secure coverage through the ACA Marketplace. Almost three in 10 (28%) adult women are part of households with low incomes (family income below 200% of the FPL was $49,720 for a family of three in 2023). Almost 4 in 10 (36%) women have completed a bachelor’s degree or higher, almost a third (27%) have a child under the age of 19 living at home, and 92% are U.S. citizens. Nearly 4 in 10 women live in the South (39%), almost a quarter (23%) live in the West, a fifth (20%) live in the Midwest, and 17% live in the Northeast (Figure 2).

What Are the Sources of Health Insurance Coverage for Women?

Copy link to What Are the Sources of Health Insurance Coverage for Women?

While most adult women have some form of either private or public health insurance, the coverage profile for those who are under and over age 65 differs considerably. For those who are under age 65, employer-sponsored coverage, individually purchased policies, and Medicaid—the state-federal program for people with low incomes—comprise the majority of coverage options. However, nearly 1 in 10 women in that age group are currently uninsured. Among women 65 years and older, the Medicare program plays a critical role covering nearly all seniors in the U.S., though often with considerable coverage gaps (such as hearing, vision and long-term services and supports) and cost-sharing burdens.

Employer-Sponsored Insurance

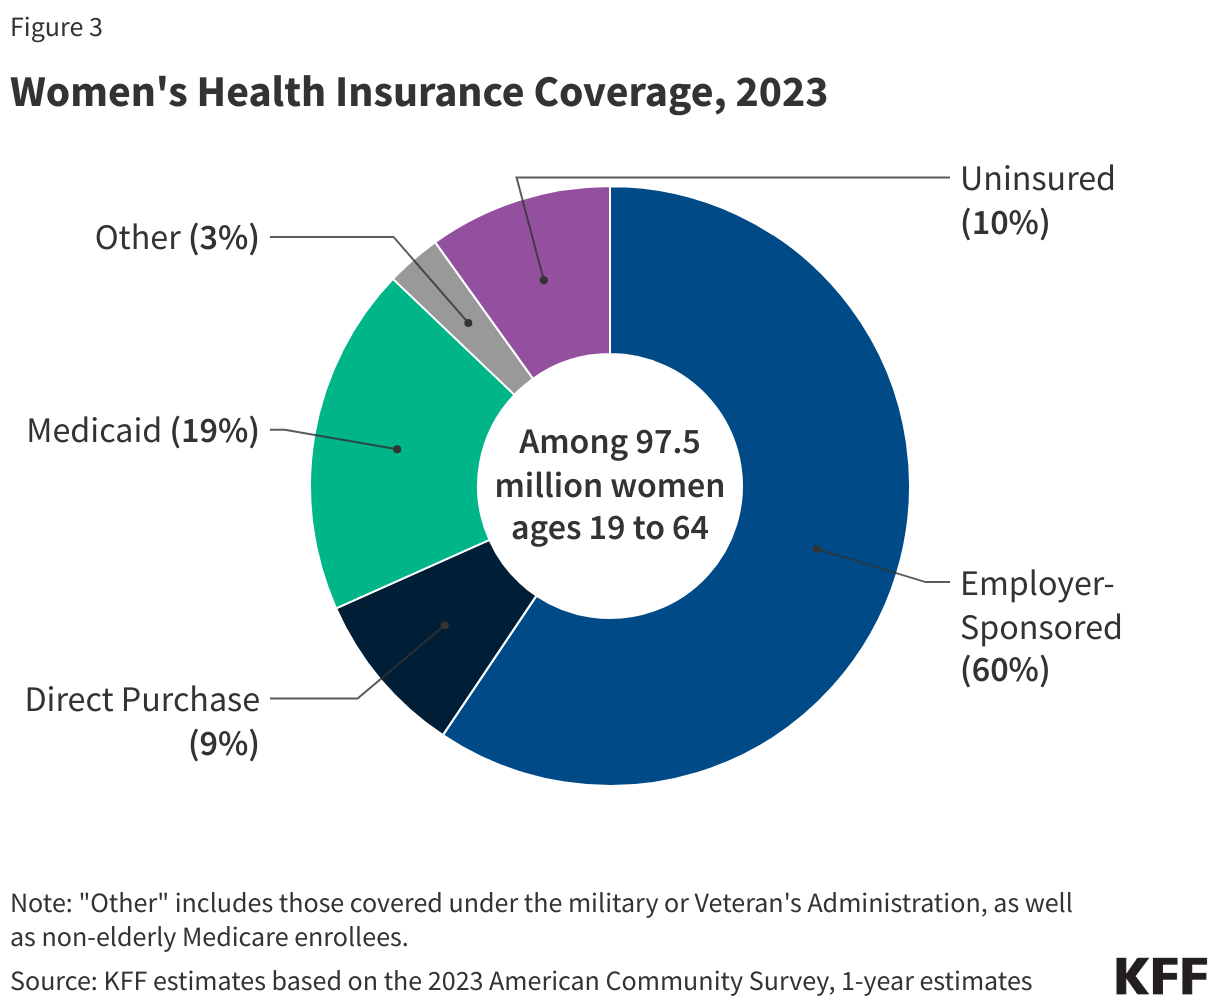
Approximately 58.3 million women aged 19-64 (60%) received their health coverage from employer-sponsored insurance in 2023 (Figure 3). Women in families with at least one full-time worker are more likely to have job-based coverage (70%) than women in families with only part-time workers (33%) or without any workers (17%).

Employer-sponsored insurance can come with substantial out-of-pocket costs based on premiums, deductibles, co-insurance, and co-payment levels. In 2023, annual insurance premiums for employer-sponsored insurance averaged $8,435 for individuals and $23,968 for families. On average, workers paid 17% of premiums for individual coverage and 29% for family coverage with the employers picking up the balance.

Women's Health Insurance Coverage, 2023 (Donut Chart)

Non-Group Insurance

In 2023, about 9% of women ages 19 to 64 (approximately 8.4 million women) and 8% of their male counterparts purchased insurance in the non-group market. This includes individuals who purchased private policies from state-based Marketplaces established under the ACA, as well as those who purchased coverage from private insurers that operate outside of the ACA Marketplaces.

Most individuals who seek insurance policies in their state’s Marketplace qualify for assistance with the coverage costs. Individuals with incomes below $58,320 (400% of the Federal Poverty Level in 2023) can receive federal tax credits which lower premium costs. The American Rescue Act (ARPA) of 2021, and subsequently the Inflation Reduction Act of 2022, have provided a temporary extension of Marketplace subsidies to people with higher income levels and led to record high enrollments in the ACA marketplace. These subsidies are set to expire at the end of 2025 and if they are not renewed, it would lead to a steep increase in insurance premium payments for ACA Marketplace enrollees. 

The ACA set new standards for all individually purchased plans and eliminated many historically discriminatory practices that affected disadvantaged women in particular. Today, plans are prohibited from charging women higher premiums than men for the same level of coverage (gender rating) or from disqualifying women from coverage because they had certain pre-existing medical conditions, including pregnancy. All direct purchase plans must also cover certain “essential health benefits” (EHBs) that fall under 10 different categories, including maternity and newborn care, mental health, and a wide range of preventive health care services. Prior to the ACA, many individual plans excluded maternity care benefits or required policyholders to purchase costly riders to obtain maternity coverage.

Medicaid

Medicaid, the state-federal program for individuals with low incomes, covered 19% of adult women ages 19 to 64 in 2023, compared to 14% of men. Historically, to qualify for Medicaid, women had to have very low incomes and be in one of Medicaid’s eligibility categories: pregnant, mothers of children 18 and younger, a person with a disability, or over 65. Women who didn’t fall into these categories typically were not eligible regardless of how low their incomes were. The ACA allowed states to broaden Medicaid eligibility to most individuals with incomes less than 138% of the FPL regardless of their family or disability status, effective January 2014. As of April 2025, 40 states and Washington, D.C. have expanded their Medicaid programs under the ACA, but 10 states have not and still base eligibility on historical categorical and income standards. For example, in Mississippi, the Medicaid income eligibility for parents is 28% of the FPL, which was approximately $6,900 for a family of three in 2023. Therefore, parents in families of three in Mississippi with incomes above this amount do not qualify for Medicaid because their income exceeds the state’s eligibility level.

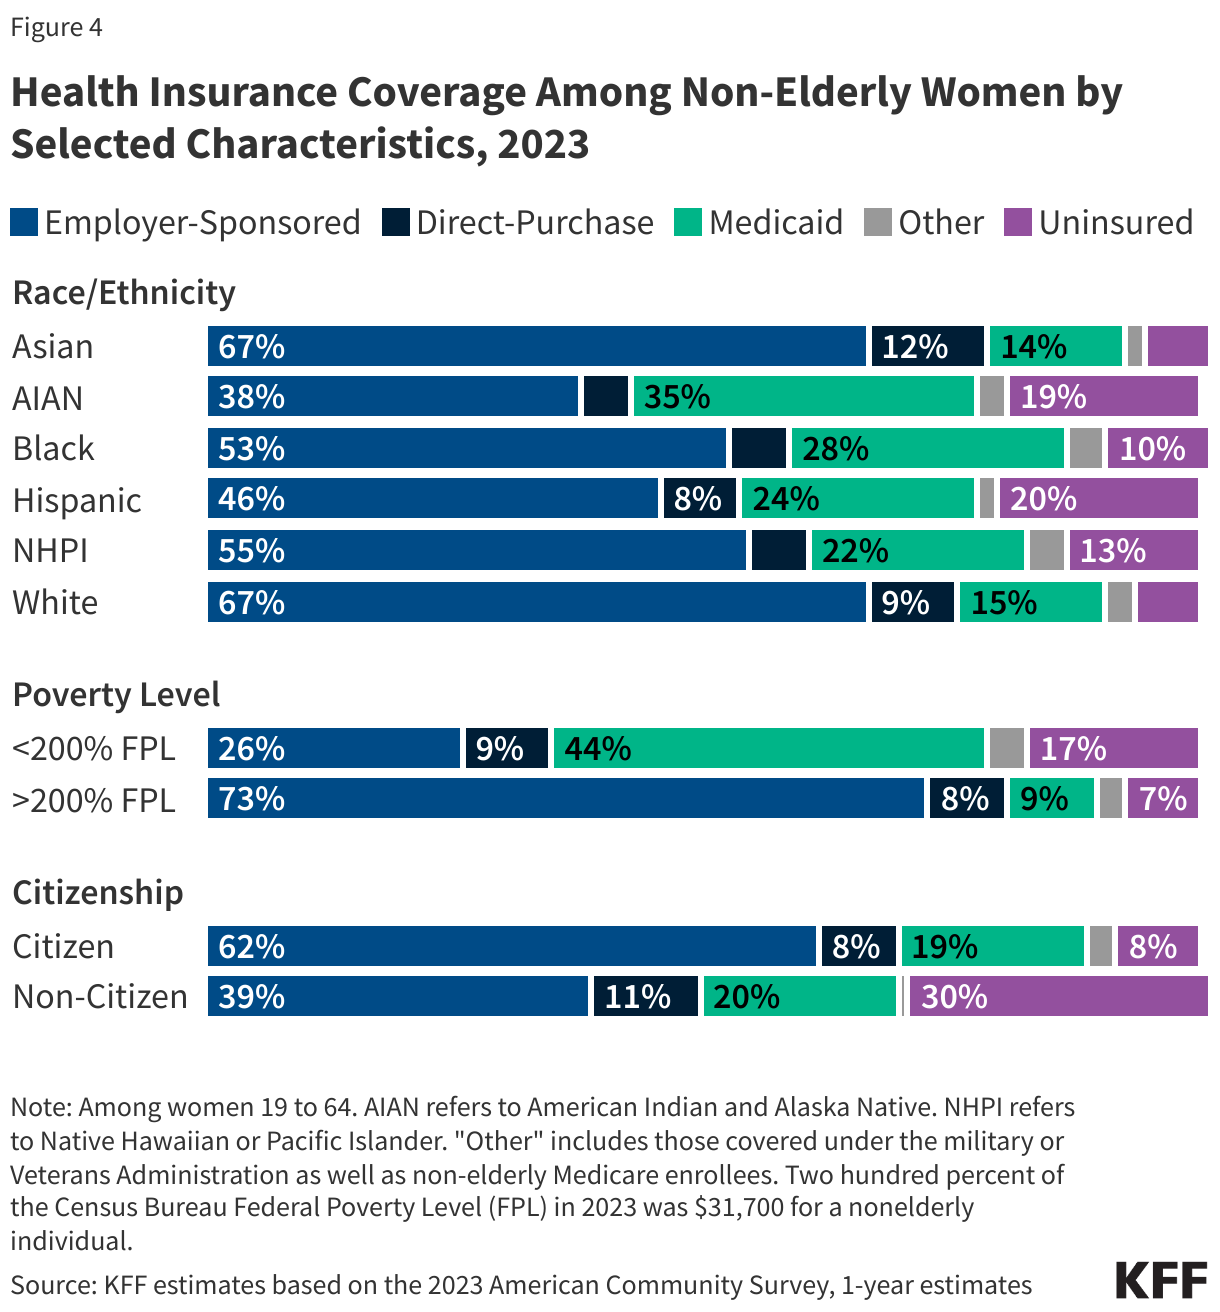
Medicaid covers the poorest segment of women in the U.S. Forty-four percent of women with incomes below 200% of the FPL and 52% of women with incomes below 100% of the FPL have Medicaid coverage.By federal law, all states must provide Medicaid coverage to pregnant women with incomes up to 133% of the FPL through 60 days postpartum. However, in recent years, there has been a growing interest in expanding the length of the postpartum coverage period and, as of April 2025, nearly all states have taken steps to extend postpartum Medicaid coverage to one year.

Medicaid covers many health services that are essential for women. Medicaid financed 41% of births in the U.S. in 2022 and accounts for 75% of all publicly-funded family planning services. State Medicaid programs are prohibited from charging any cost-sharing for pregnancy-related care or family planning services. Over half of states have established programs that use Medicaid funds to cover the costs of family planning services for women with low incomes who remain uninsured, and most states have limited scope Medicaid programs to pay for breast and cervical cancer treatment for certain uninsured women with low incomes. Conversely, coverage for abortion is very limited under Medicaid as a result of the Hyde Amendment, a rider to federal appropriations that bans any federal funds from being used to pay for abortions unless the pregnancy is determined to be a result of rape or incest or poses a threat to the pregnant person’s life (more on abortion in the following section).

Uninsured Women

In 2023, approximately 10% of non-elderly women (9.3 million) were uninsured. This rate is slightly lower than that of men (13%) because, on average, women have lower incomes and have been more likely to qualify for Medicaid than men under one of Medicaid’s eligibility categories: pregnant, parent of children under 18, disability, or over 65. The ACA opened the door for states to eliminate the categorical requirements, but the gender gap in the insured rates between men and women persists.

The disadvantage uninsured individuals experience in accessing care and health outcomes is well established. Compared to women with insurance, those who are uninsured have lower use of important preventive services such as mammograms, Pap tests, and timely blood pressure checks. They are also less likely to report having a regular doctor, which is associated with better access to care and higher rates of use of recommended preventive services.

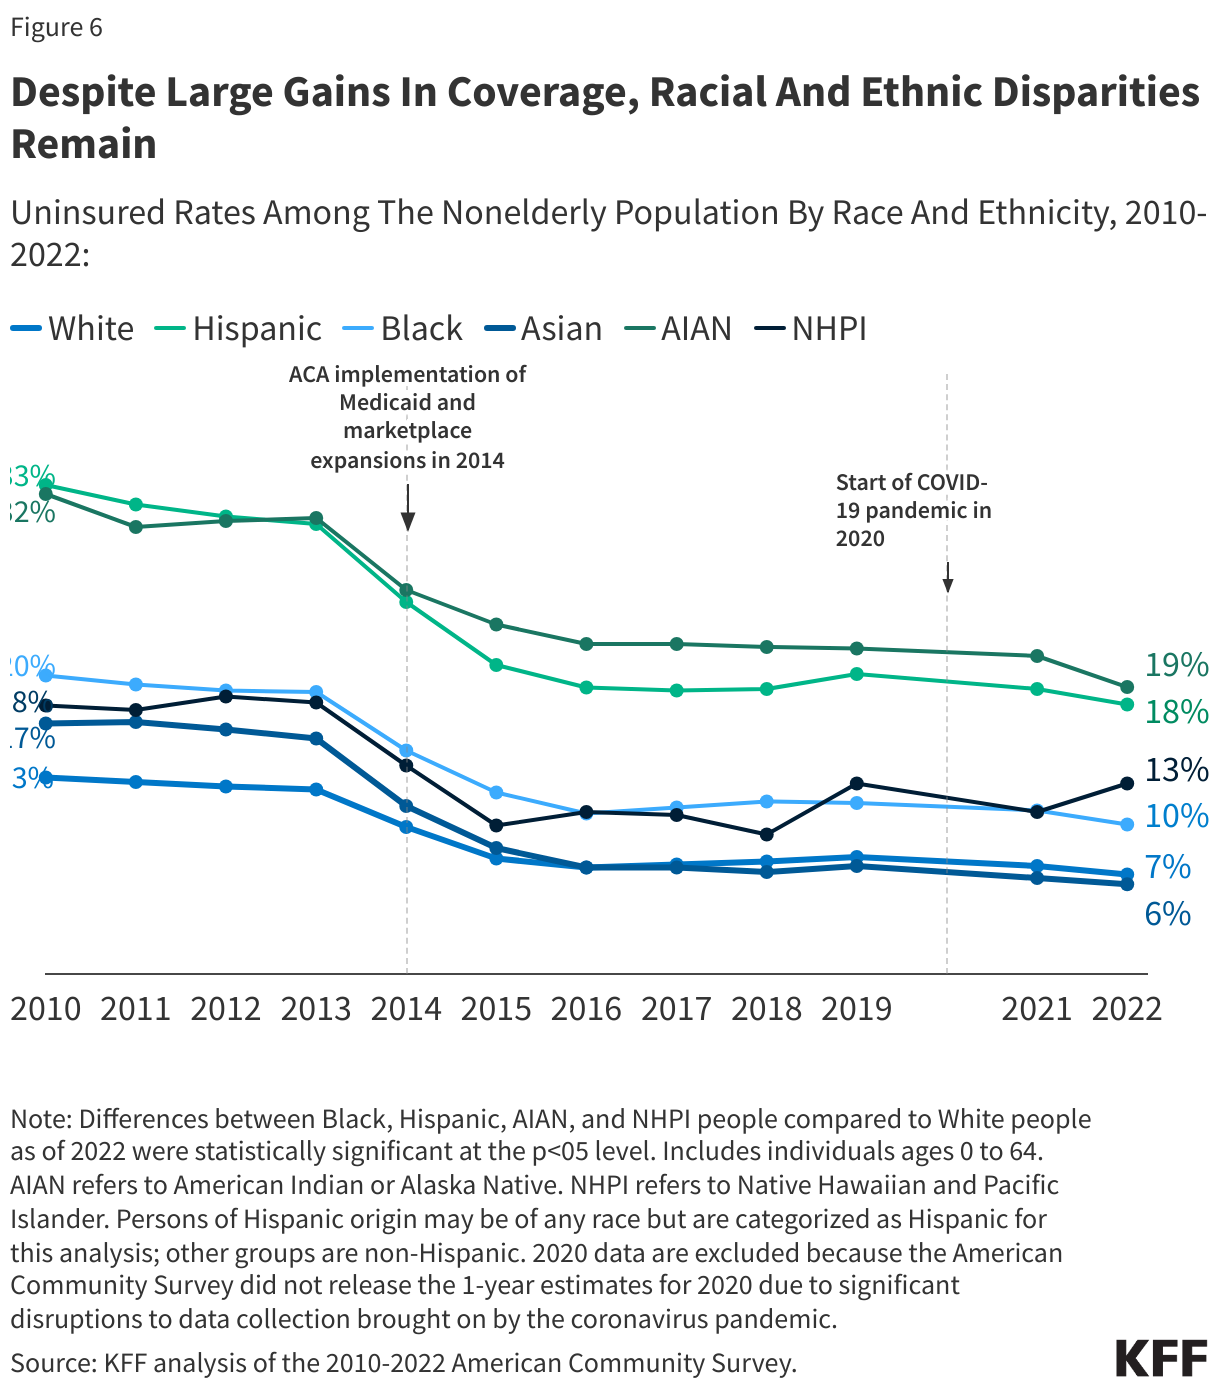
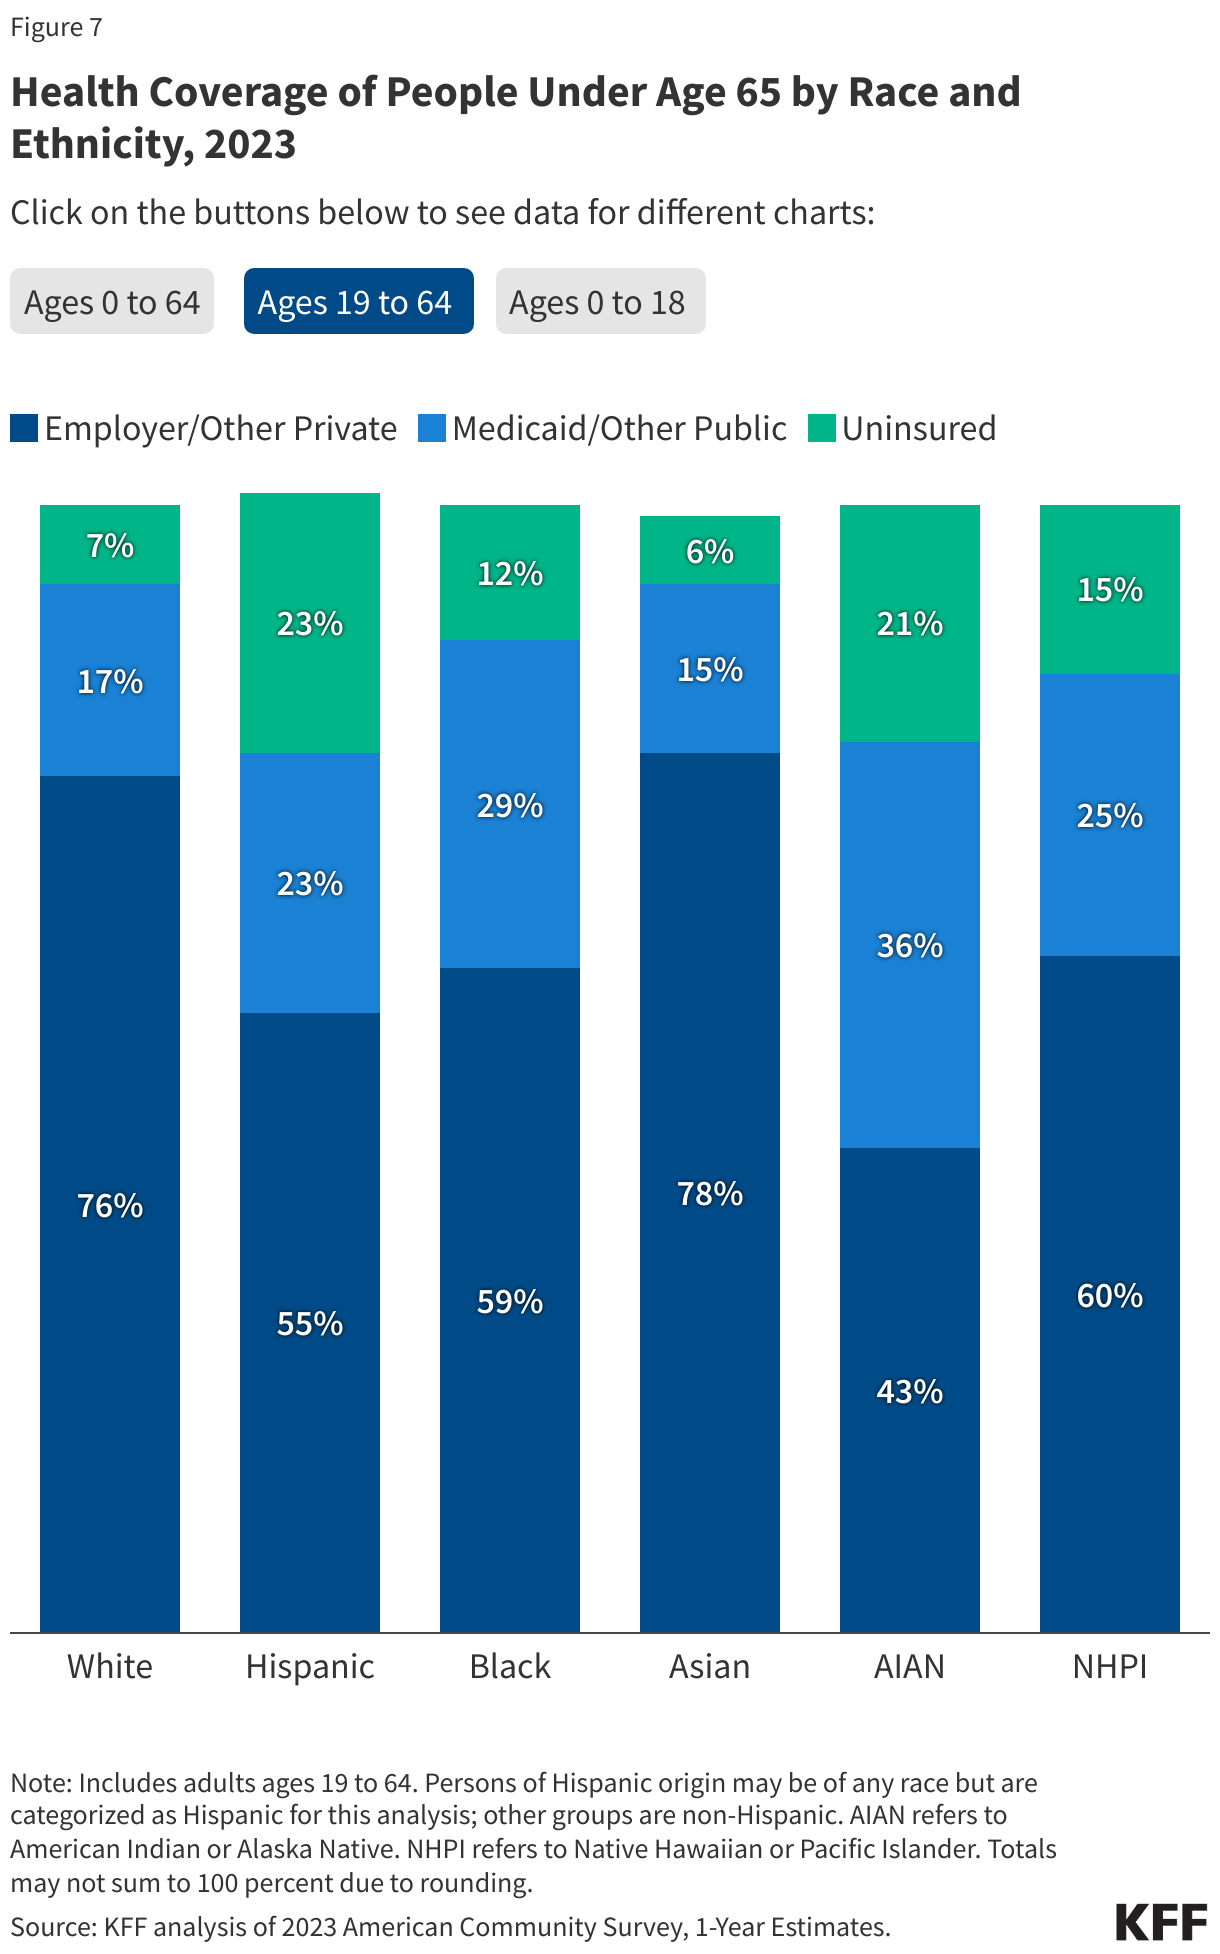
Women with lower incomes, women of color, and non-citizen women are at greater risk of being uninsured (Figure 4). One in 5 Hispanic (20%) and American Indian and Alaska Native (19%) women and 17% of women with incomes under 200% of the FPL are uninsured. A higher share of single mothers are uninsured (10%) than women in two-parent households (7%) (data not shown). Most uninsured women live in a household where someone is working; 69% are in families with at least one adult working full-time; and 82% are in families with at least one part-time or full-time worker (data not shown).

Health Insurance Coverage Among Non-Elderly Women by Selected Characteristics, 2023 (Stacked Bars)

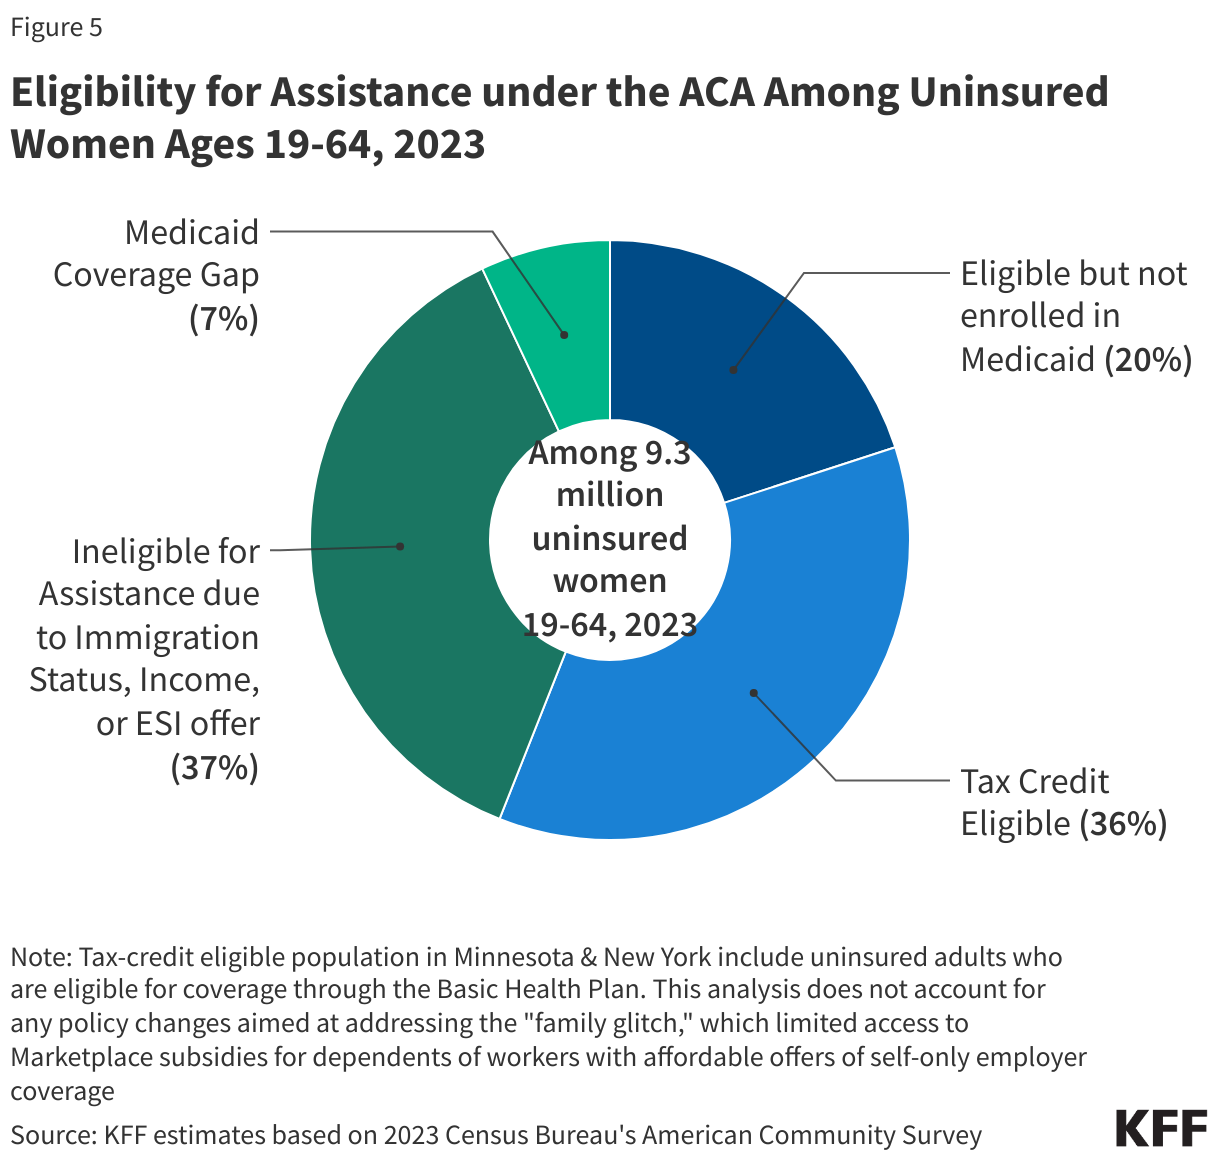
Many women who are uninsured are eligible for financial assistance with the costs of coverage. A fifth of uninsured women (20%) are eligible for Medicaid coverage but are not enrolled in the program (Figure 5). Over a third of uninsured women (36%), about 3.3 million women, qualify for subsidies to cover the premium costs and some of the out-of-pocket costs of Marketplace plans but may not be aware of coverage options or may face barriers to enrollment. However, 7% of uninsured women live in states that have not adopted the ACA Medicaid expansion and fall into a “coverage gap” because their incomes are above the thresholds to qualify for Medicaid but below the levels to qualify for Marketplace tax credits (below 100% of the FPL). Another 1 in 3 (37%) uninsured women are not eligible for any assistance with health coverage due to their immigration status, their income, or because they have an offer of coverage from their employer.

Eligibility for Assistance under the ACA Among Uninsured Women Ages 19-64, 2023

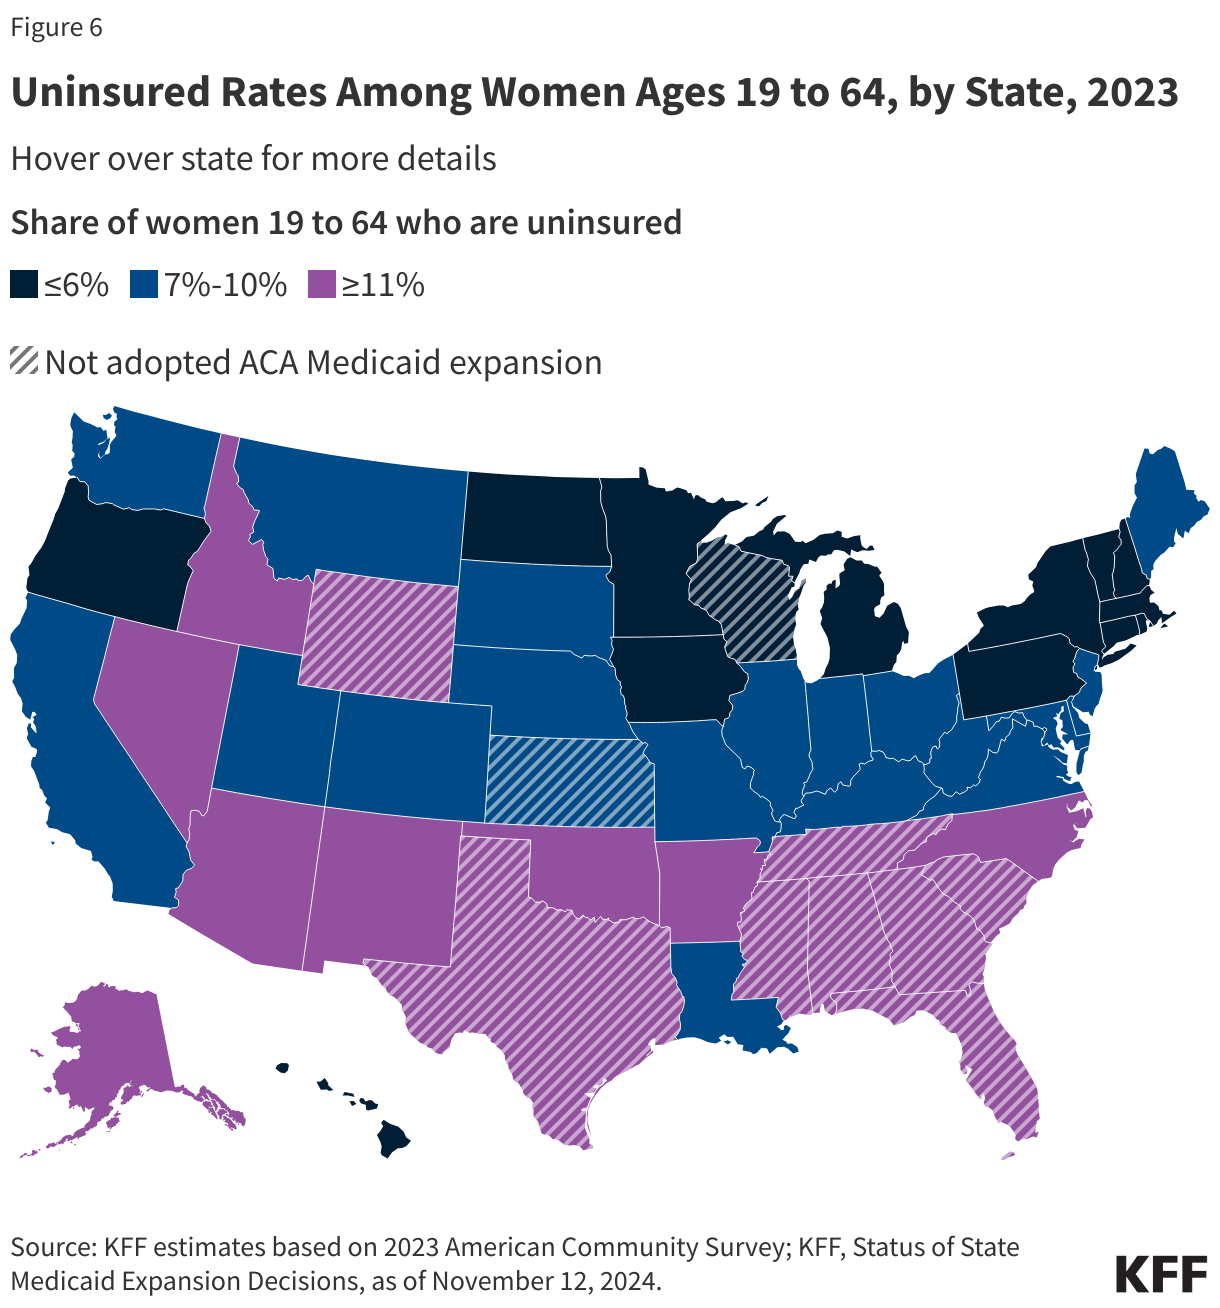
There is considerable state-level variation in uninsured rates across the nation, ranging from 20% of women in Texas to 3% of women in Washington D.C., Hawaii, Massachusetts, and Vermont (Figure 6). Of the 16 states with uninsured rates above the national average (10%), eight have not adopted the ACA Medicaid expansion.

Uninsured Rates Among Women Ages 19 to 64, by State, 2023 (Choropleth map)

Medicare

Medicare is the federal program that provides health coverage to virtually all people ages 65 and older as well as younger people with long-term disabilities. In 2020, Medicare covered 35 million women, including nearly 31 million ages 65 and older, and over 4 million under age 65 with long-term disabilities.

More than half (55%) of all Medicare beneficiaries are women and 45% are men. The population of women covered by Medicare is diverse, with varying social, economic, and health circumstances. Women live longer than men on average (80 years vs. 75 years life expectancy at birth in 2022), and many live with certain chronic illnesses, cognitive and mental impairments, and functional problems at higher rates than men. A higher share of older women than men also experience urinary incontinence, depression, osteoporosis, pulmonary disease, and Alzheimer’s/dementia. Medicare plays a key role in supporting the health and well-being of women, covering a broad range of essential services, including preventive, primary and specialty care, and prescription drugs. However, reflecting Medicare’s original role as a program to serve the medical needs of older adults, coverage of services for enrollees of reproductive age may be more limited. For example, there is no federal requirement for Medicare to cover all contraceptive services and supplies for the purpose of preventing pregnancy for younger Medicare enrollees with permanent disabilities.

Another gap in the Medicare program is the absence of coverage for long-term care services and supports (LTSS), such as nursing home stays and home care services, which many older adults need and seek but are expensive and unaffordable for some. Compared with men, women are more likely to require these services because they have more chronic conditions, have higher rates of physical and cognitive impairments, and are more likely to live alone. Medicare only covers time-limited LTSS after a hospitalization and does not cover ongoing LTSS for those with chronic conditions or functional impairments. Some older women can qualify for Medicaid for LTSS, but only if they have low incomes and, in some cases, must spend down most of their assets. Just a small share of seniors have private long-term care insurance to help cover some of the costs of LTSS. As a result, unless they have incomes low enough to qualify for Medicaid, many older people do not have any coverage for LTSS and rely on unpaid caregiving provided by family, friends, or neighbors. The majority of informal caregivers are women, who are most commonly caring for aging parents and spouses.

Women with Medicare also tend to have more modest incomes than men—a consequence of smaller lifetime savings, lower retirement income, and divorce and widowhood that result in only one income. While Medicare covers many necessary health care services, gaps in benefits, cost-sharing requirements, and spending on premiums for Medicare and supplemental coverage can translate into high out-of-pocket expenses for some people in the program. In 2020, 13% of women and 11% of men with Medicare reported that they had faced cost-related challenges in the past 12 months, such as trouble getting care due to cost or problems paying medical bills. These challenges are more common among female Medicare enrollees who are Black (22%) and Hispanic (18%), do not have a bachelor’s degree (15%), and those with annual incomes below $20,000 (20%).

How Do Health Care Costs and Scope of Benefits Affect Women’s Access to Care?

Copy link to How Do Health Care Costs and Scope of Benefits Affect Women’s Access to Care?

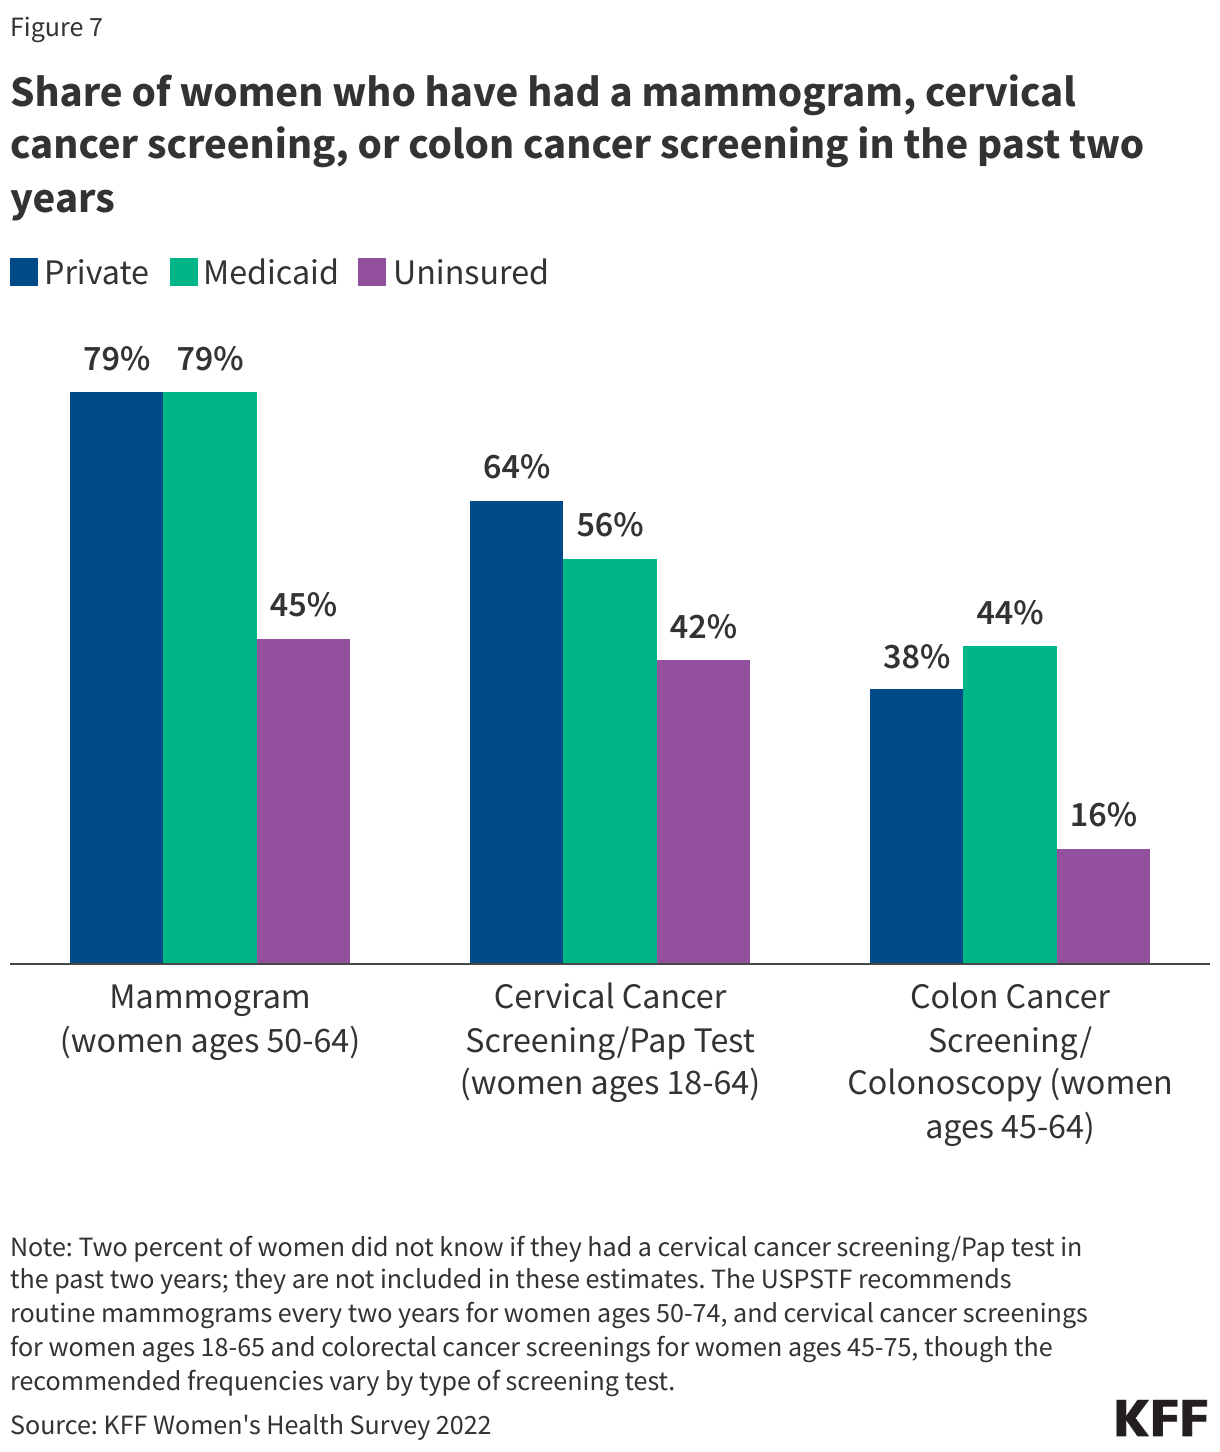
The ACA set national standards for the scope of benefits offered in private plans. As mentioned earlier, many insurance plans had adopted practices that discriminated against women that were addressed in the ACA. In addition to the broad categories of essential health benefits (EHBs) offered by Marketplace plans, all privately purchased plans must cover maternity care, which had been historically excluded from most individually purchased plans requiring the purchase of an expensive rider for that benefit to be covered. In addition, most private plans must cover preventive services without co-payments or other cost sharing. This includes screenings for breast and cervical cancers, well-woman visits (including prenatal visits), prescribed contraceptives, breastfeeding supplies and supports such as breast pumps, and several services for sexually transmitted infections (STI). Higher shares of women with private and Medicaid coverage report having had recommended preventive services such as mammograms, Pap screenings or colonoscopies compared to those who were uninsured (Figure 7).

Share of women who have had a mammogram, cervical cancer screening, or colon cancer screening in the past two years

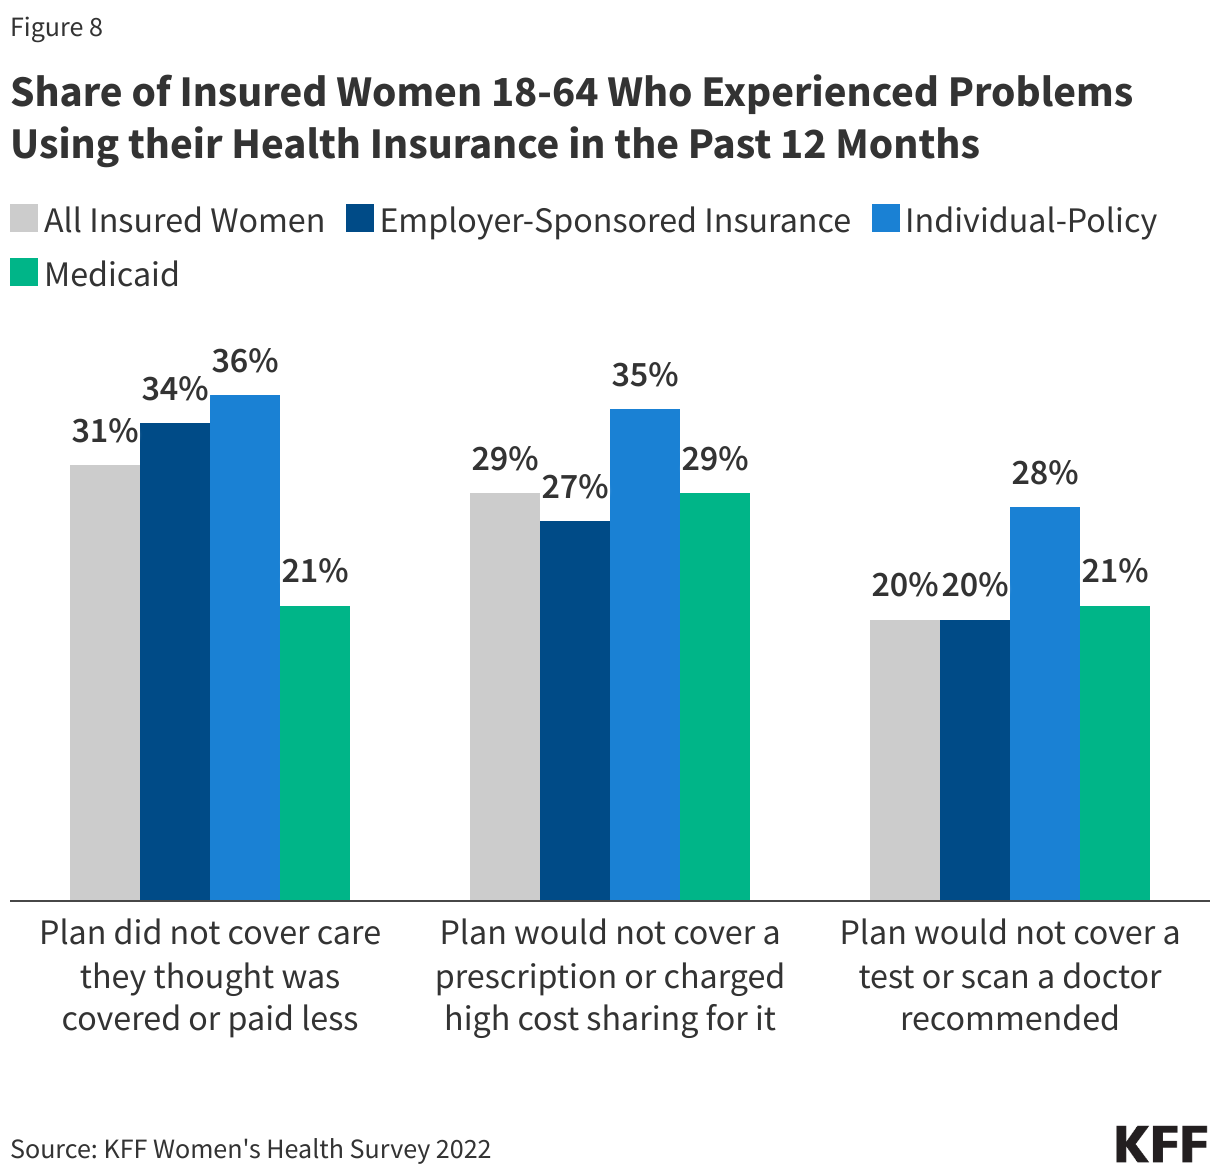
Affordability of coverage continues to be a significant concern for many women, both for those who are uninsured as well as those with coverage. The leading reason why uninsured adults report that they have not obtained coverage is that it is too expensive. Under employer-sponsored insurance, the major source of coverage for women, 61% of all covered workers with a general annual deductible have deductibles of at least $1,000 for single coverage. Despite having coverage, many insured women (31%) report that their plans did not always cover all of their needed care or paid less than they expected (Figure 8).

Share of Insured Women 18-64 Who Experienced Problems Using their Health Insurance in the Past 12 Months (Grouped column chart)

What Are the Issues Affecting Women's Care and Access?

Copy link to What Are the Issues Affecting Women's Care and Access?

Reproductive Health

Pregnancy

Maternity Care

In 2023, there were approximately 3.6 million births in the U.S. Childbirth is the leading reason for hospitalization, and most private insurance plans and the Medicaid program are required to cover care associated with childbirth. Medicaid covers about 4 in 10 births nationally and, in some states, more than half. The Medicaid program prohibits plans from charging out-of-pocket charges for pregnancy-related care, and coverage lasts through one year postpartum in most, but not all, states. For people with private insurance, which finances just over half of  births (51%), the federal Pregnancy Discrimination Act requires employer plans to cover maternity care benefits. However, even for those with private insurance, a pregnancy often comes with significant out-of-pocket health expenses that can reach thousands of dollars. A KFF analysis estimated that women enrolled in large group plans pay around $3,000 out-of-pocket for costs associated with pregnancy, childbirth, and post-partum care. On average, Caesarean section births, which account for approximately one-third of births in the U.S., are significantly more expensive than vaginal deliveries. The ACA also requires individual plans to cover maternity care and bans plans from implementing restrictions on coverage of pre-existing health conditions, including pregnancy.

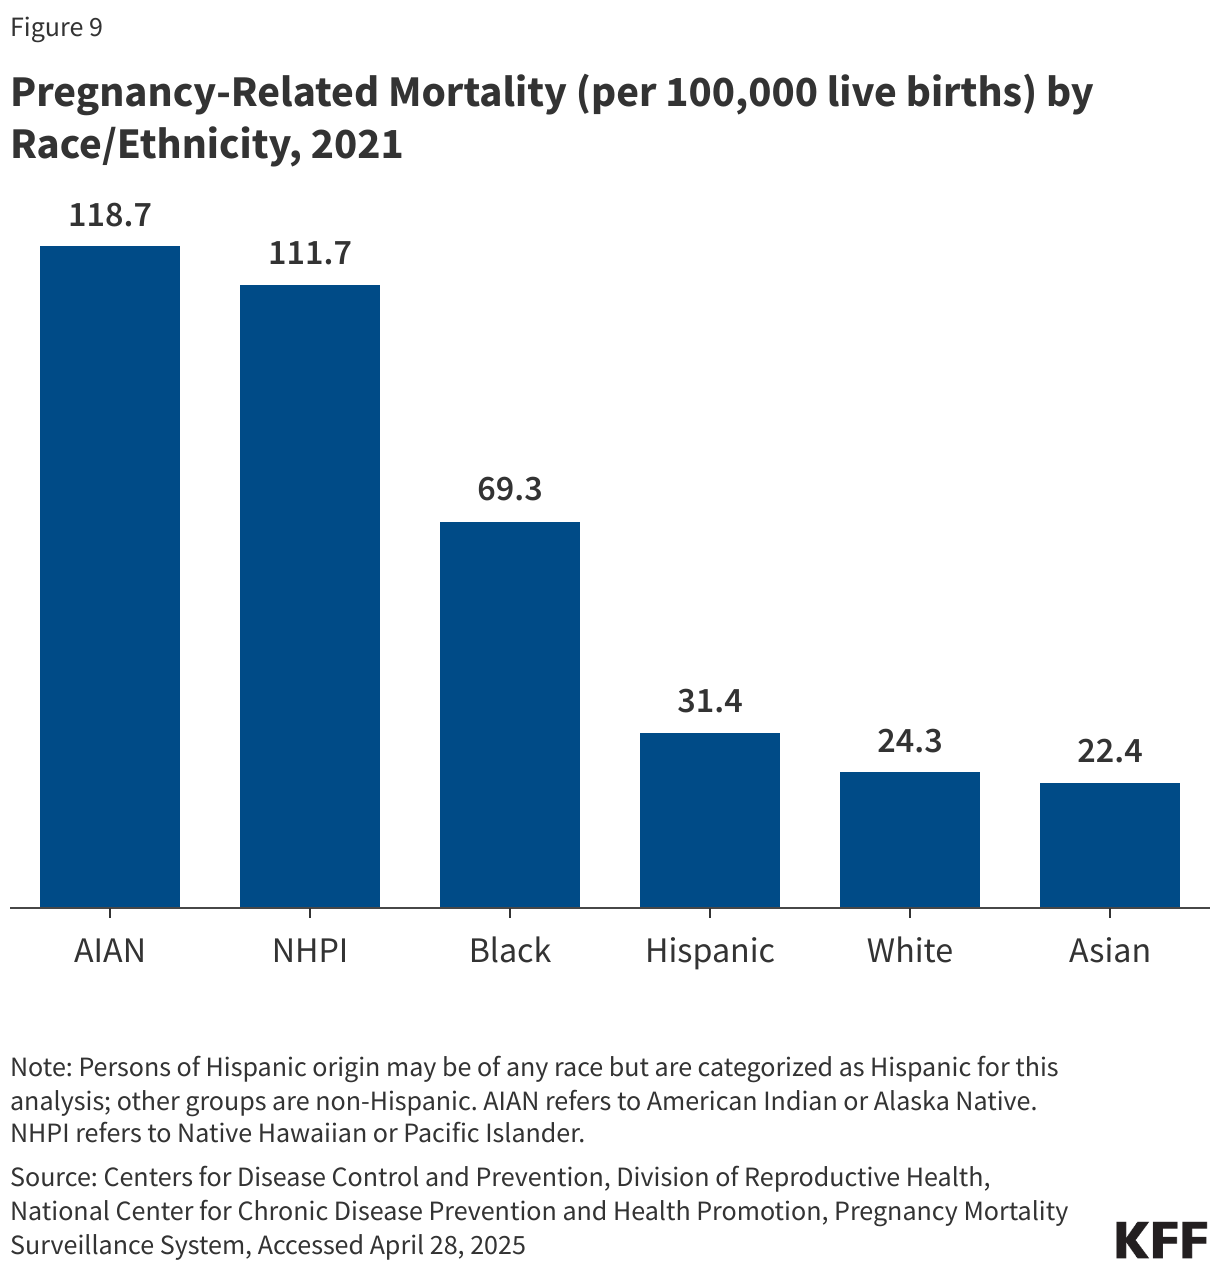
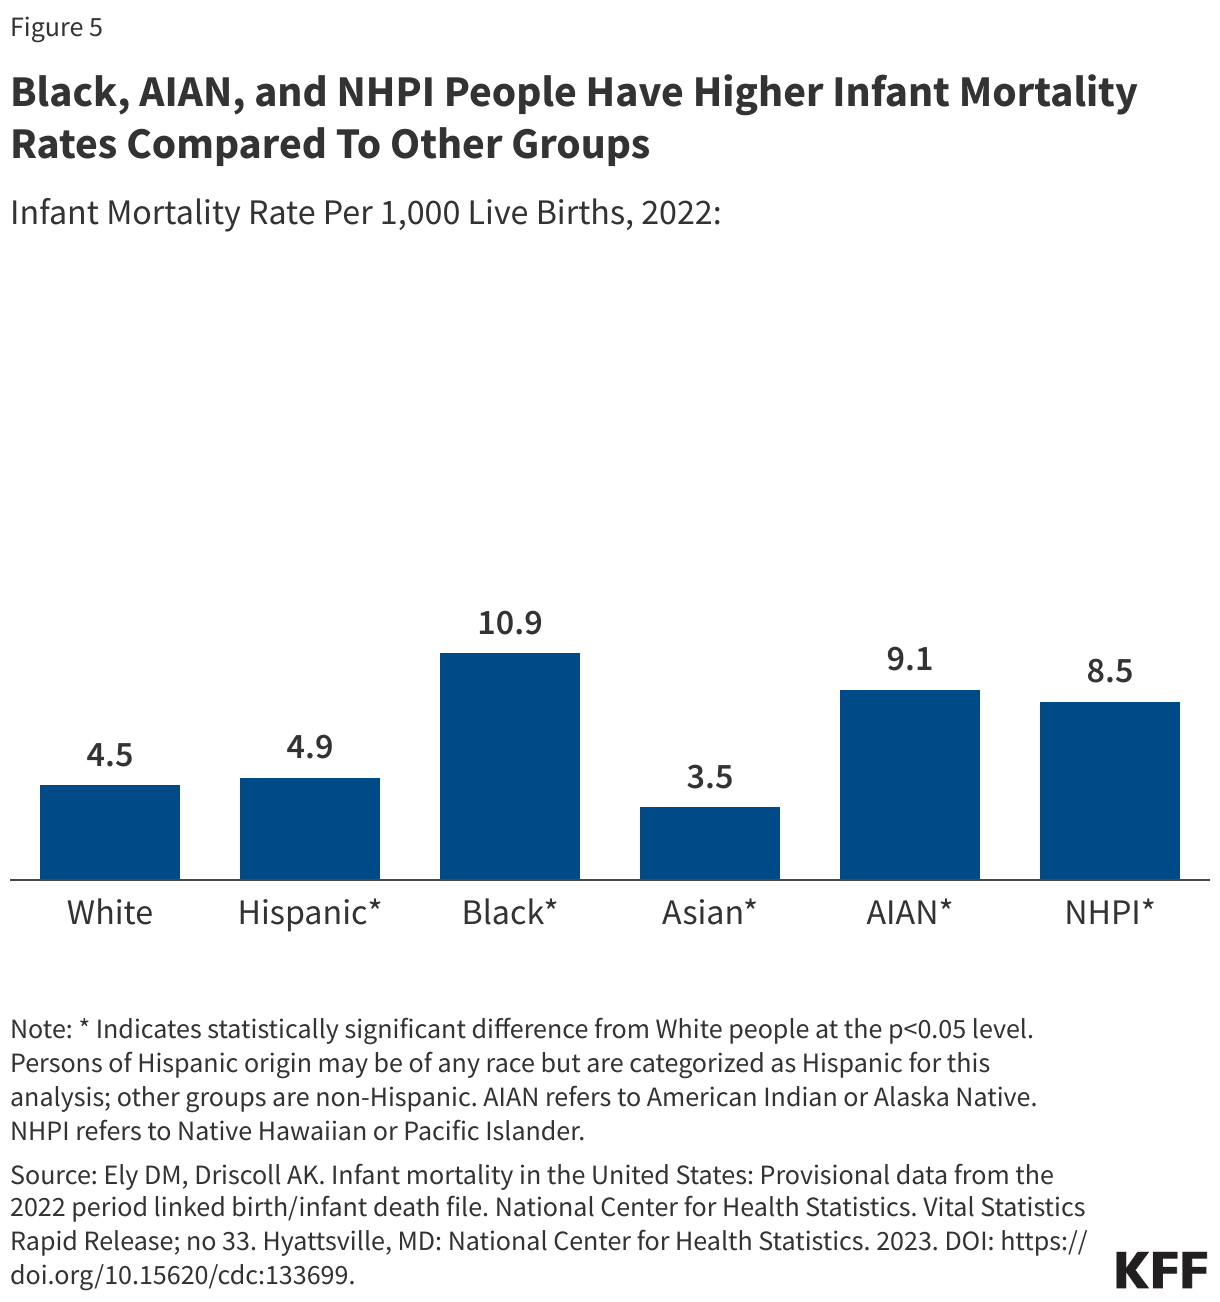
In recent years, there has been growing attention to pregnancy-related quality of care and maternal health. Maternal and infant mortality rates in the U.S. are far higher than those in similarly large and developed countries, and people of color are at a considerably higher risk for poor maternal and infant health outcomes compared to their White peers. Despite continued advancements in medical care, rates of maternal mortality and morbidity and preterm birth have been rising in the U.S., characterized by stark racial disparities. Notably, rates of pregnancy-related death (deaths within one year of pregnancy) among American Indian and Alaska Native (AIAN), Native Hawaiian or Pacific Islander (NHPI) and Black women are over four to two times higher, respectively, compared to the rate for White women (118.7, 111.7, 69.3 and 24.3 per 100,000 live births, respectively) (Figure 9). The Centers for Disease Control (CDC) has determined that many of these pregnancy-related deaths were preventable, caused by cardiac-related conditions, infection, hemorrhage, and mental health conditions, including substance use. Maternal death rates increased during the COVID-19 pandemic and racial disparities widened for Black women. Black, AIAN, and NHPI women also have higher shares of preterm births, low birthweight births, or births for which they received late or no prenatal care compared to White women. Infants born to Black, AIAN, and NHOPI people have markedly higher mortality rates than those born to White women.

Pregnancy-Related Mortality (per 100,000 live births) by Race/Ethnicity, 2021

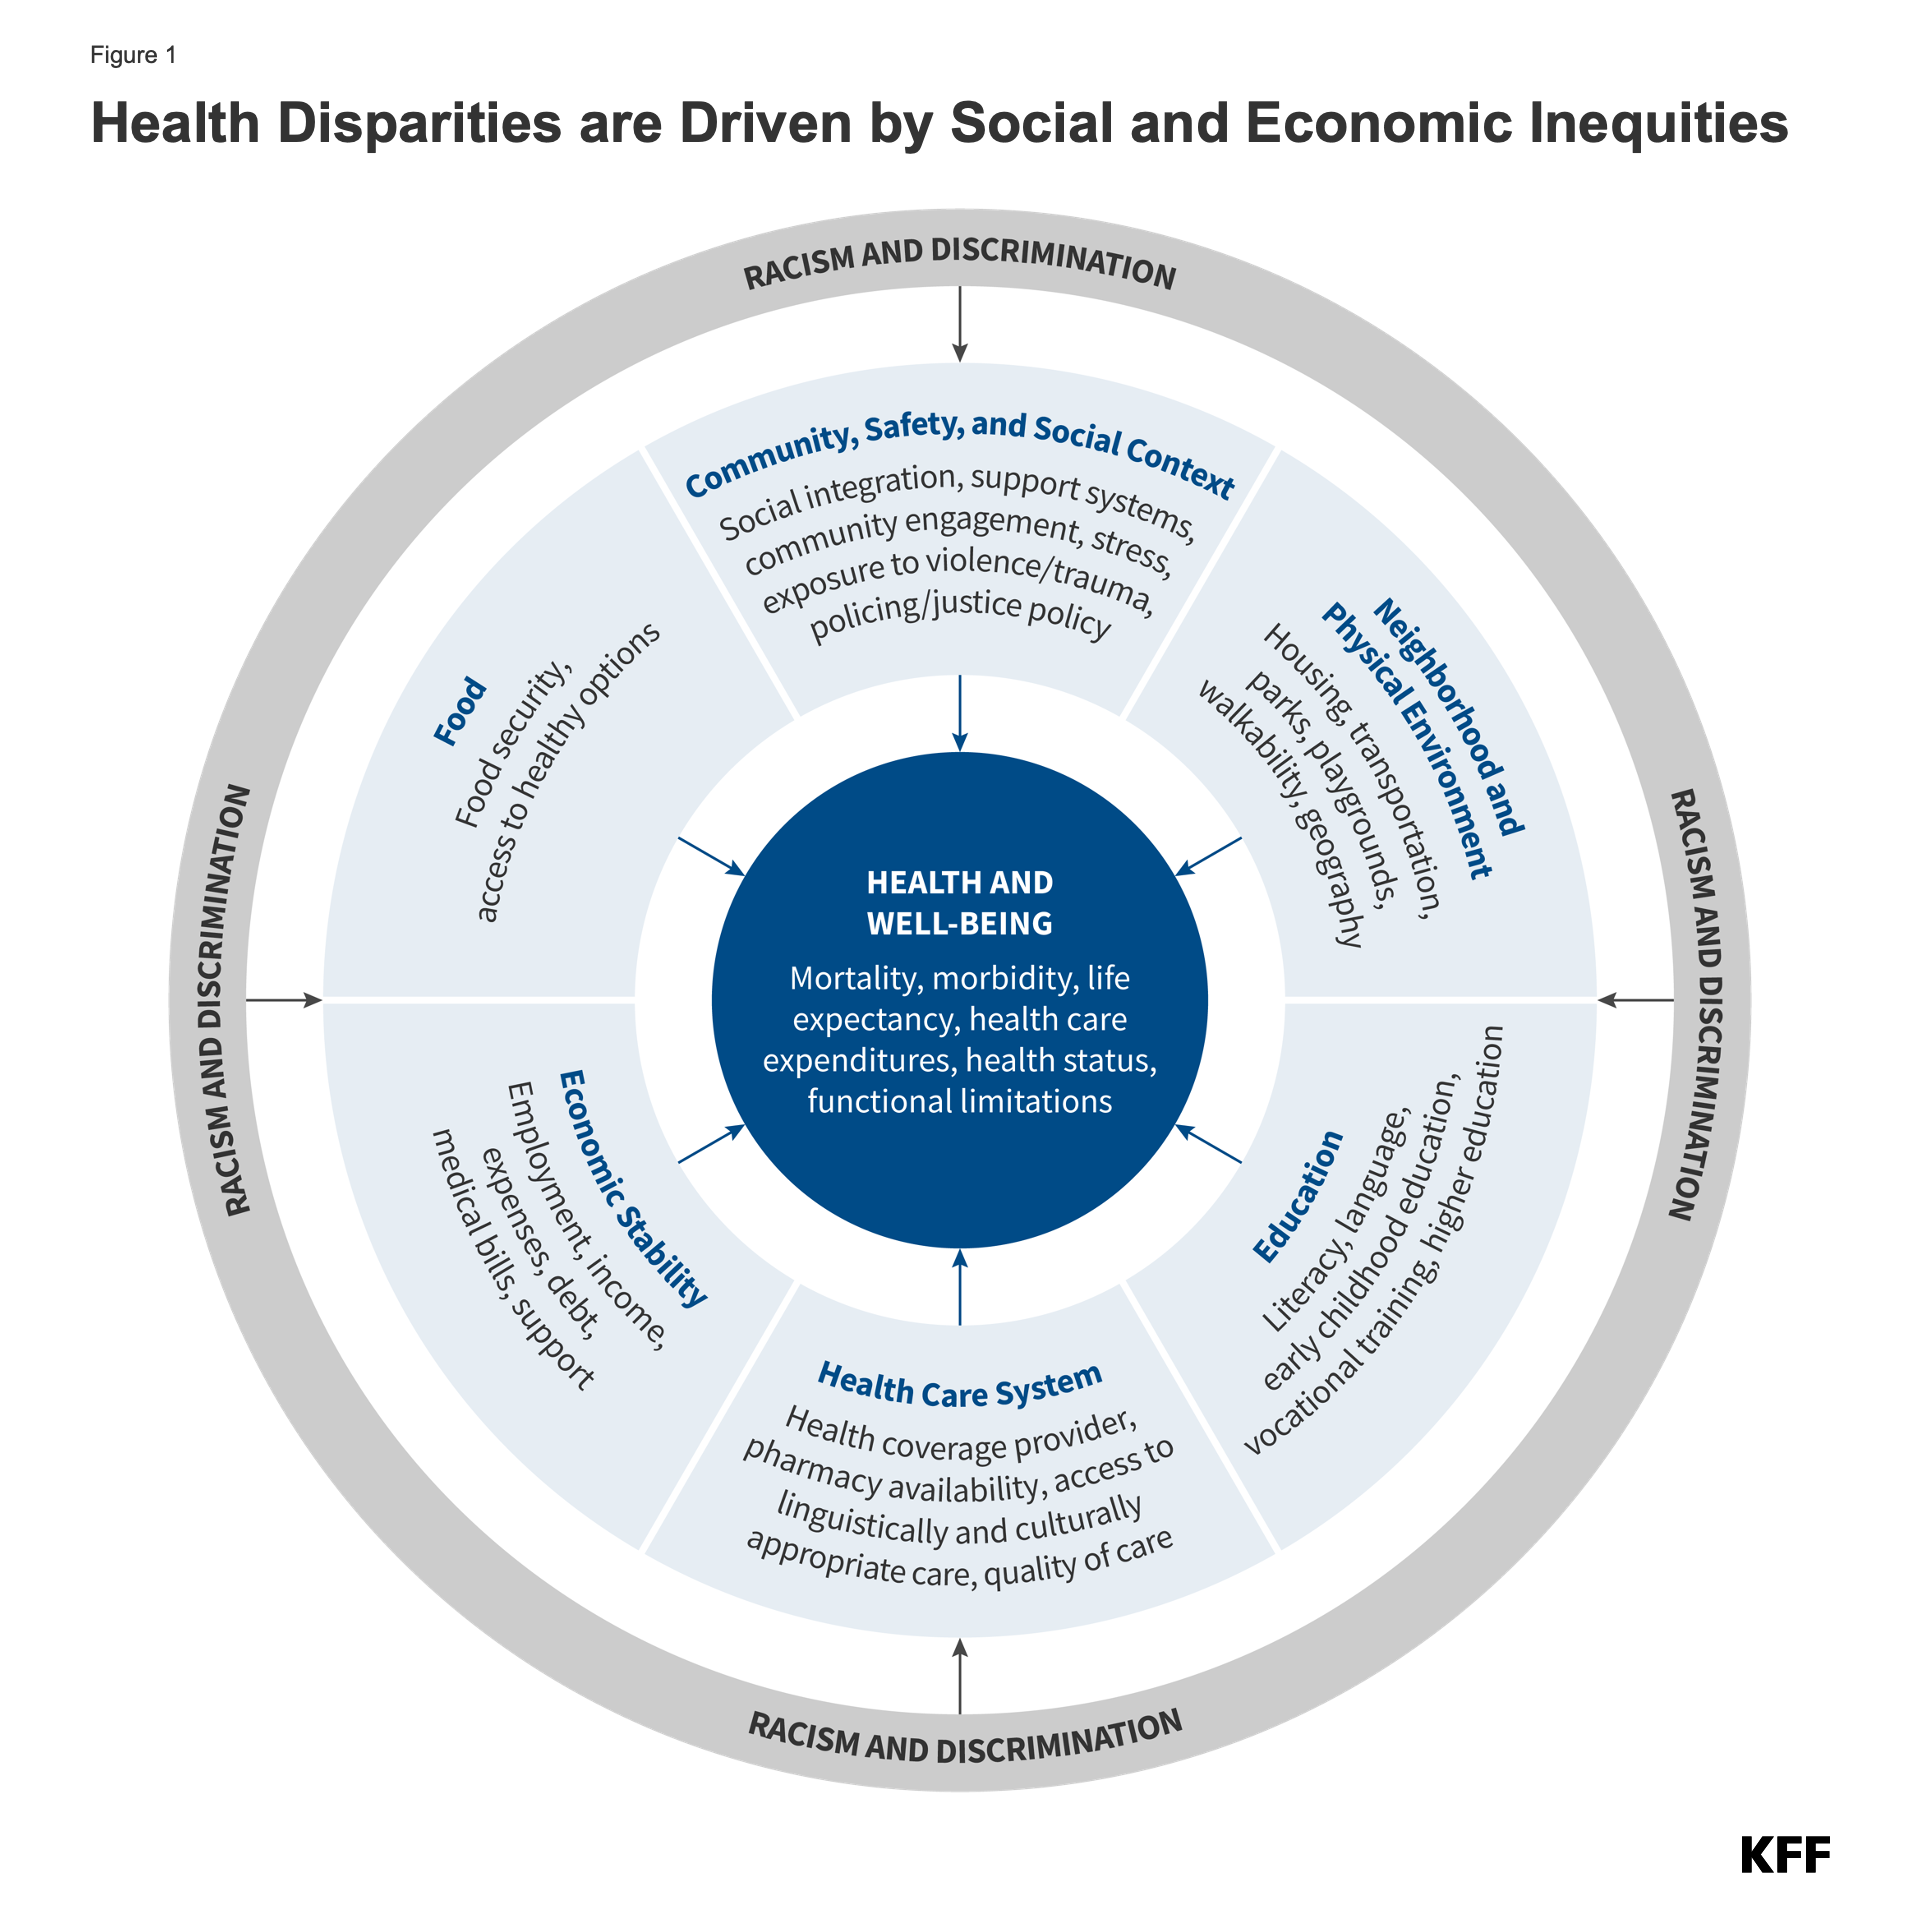
The disparities in maternal and infant health are symptoms of broader underlying social and economic inequities that are rooted in racism and discrimination. Differences in health insurance coverage and access to care play a role, but notably, disparities in maternal and infant health persist even when controlling for certain underlying social and economic factors, such as education and income, pointing to the roles racism and discrimination play in driving disparities. Moreover, with the overturning of Roe v. Wade and the numerous states that have enacted abortion bans across the nation, increased barriers to abortion for people of color may widen the already existing large disparities in maternal and infant health.

There have been efforts at the policy level and in clinical circles to improve maternal health and address disparities. At the state and local levels, multidisciplinary maternal mortality review committees and perinatal quality collaboratives have focused on data collection and reviewing the causes behind pregnancy-related deaths in their communities to try to prevent deaths in the future.

Fertility Assistance

Many people require fertility assistance to have children. These services include diagnostic services, treatment services, and fertility preservation. People seek fertility assistance for several reasons, such as if they or their partner has infertility, or because they are in a same-sex relationship or are single and desire children. Both female and male factors contribute to infertility, including problems with ovulation (when the ovary releases an egg), structural problems with the uterus or fallopian tubes, problems with sperm quality or motility, and hormonal factors. About 25% of the time, infertility is caused by more than one factor, and in about 10% of cases, infertility is unexplained. Infertility estimates, however, do not account for LGBTQ+ or single individuals who may also need fertility assistance for family building. Thus, there are varied reasons that may prompt individuals to seek fertility care.

Despite a need for fertility services, fertility care in the U.S. is inaccessible to many due to the cost. Fertility treatments are expensive and often are not covered by insurance. While some private insurance plans cover diagnostic services, there is very little coverage for costly treatment services such as intrauterine insemination, in vitro fertilization, and cryopreservation.

Most people who use fertility services must pay out of pocket, with costs often reaching thousands of dollars depending on the services received. This means that in the absence of insurance coverage, fertility care is out of reach for many people. Few states require private insurance plans to cover fertility assistance services, but these only apply to a subset of insurance plans and beneficiaries. Additionally, even fewer states have any fertility coverage requirement under Medicaid, the health coverage program for people with low incomes. The Trump Administration has issued an executive order requesting policy recommendations to protect access and reduce the costs for IVF, but Congressional action is required to meaningfully expand options to cover IVF services for the vast majority of people.

Abortion

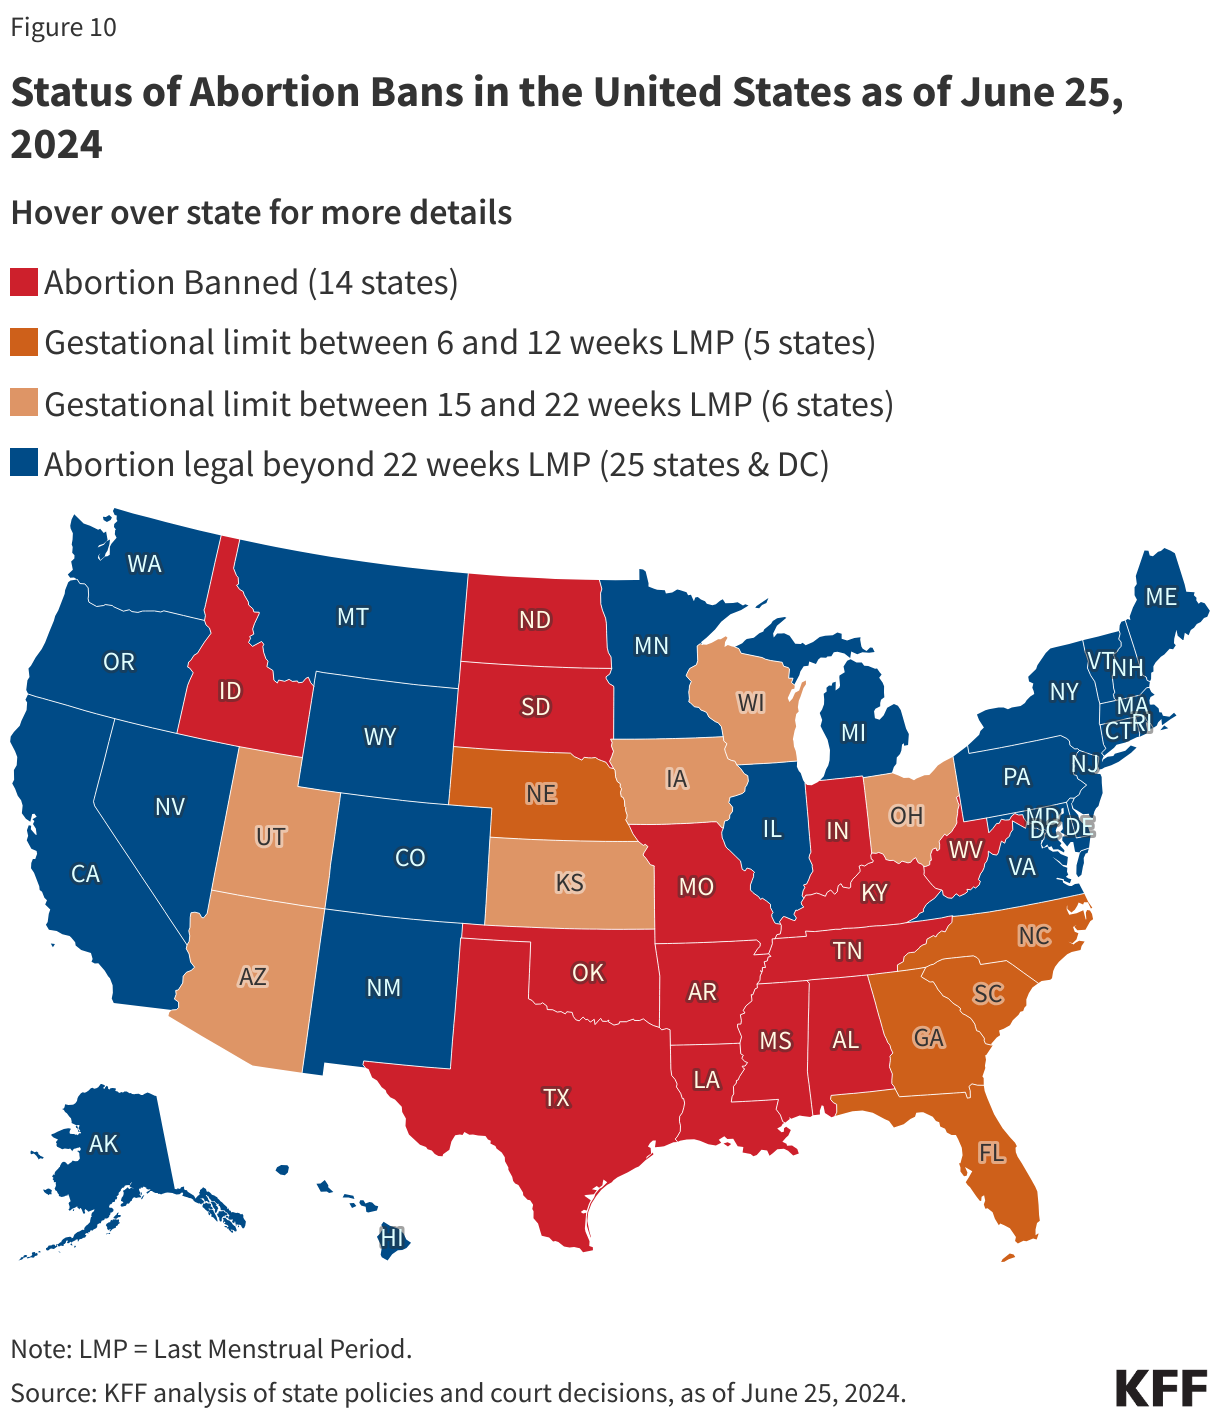
Nearly 1 in 4 women in the U.S. have an abortion in their lifetime. Starting with the 1973 landmark Supreme Court ruling in Roe v. Wade, women in the U.S. had the right to abortion up until the point of viability, regardless of where they lived. On June 24, 2022, the Supreme Court issued a ruling in Dobbs v. Jackson Women’s Health Organization that overturned the constitutional right to abortion as well as the federal standards of abortion access, established by prior decisions in the cases Roe v. Wade and Planned Parenthood v. Casey. The Dobbs decision allows states to set policies regarding the legality of abortions and establish gestational limits. Access to and availability of abortions vary widely between states, with large swaths of the country banning or restricting almost all abortions, with few exceptions, and some states enshrining and protecting abortion rights (Figure 10).

Map of the United States showing the status of abortion bans as of May 7, 2025

Abortion banned in 12 states: Alabama, Arkansas, Idaho, Indiana, Kentucky, Louisiana, Mississippi, Oklahoma, South Dakota, Tennessee, Texas, West Virginia

Gestational limit between 6 and 12 weeks LMP in effect in 6 states: Florida (6 weeks), Georgia (6 weeks), Iowa (6 weeks), Nebraska (12 weeks), North Carolina (12 weeks), South Carolina (6 weeks).

Gestational limit between 15 and 22 weeks LMP in effect in 4 states: Iowa, Kansas, Ohio, and Utah

Gestational limit at or between viability (19 states): California, Connecticut, Delaware, Hawaii, Illinois, Maine, Massachusetts, Missouri, Montana, Nevada, New Hampshire, New York, North Dakota, Pennsylvania, Rhode Island, Vermont, Virginia, Washington, Wyoming

No gestational limit (9 states  & DC): Alaska, Colorado, DC, Maryland, Michigan, Minnesota, New Jersey, New Mexico, Oregon, Vermont

There are different types of abortion methods, broadly divided into procedures such as a dilation and evacuation (D&E) or dilation and curettage (D&C) and medication, which typically involves two pills – mifepristone and misoprostol. The Guttmacher Institute estimates that approximately two-thirds (63%) of all abortions are medication abortion, which can be provided by a clinician in person or by telehealth when the pills are mailed or dispensed at a retail pharmacy. Telehealth abortion care has grown in recent years, and now account for one in four abortions in the U.S.

Decades of research have shown that abortion is a very safe medical service. Still, despite its strong safety profile, abortion is the most highly regulated medical service in the country and is now banned or restricted to early gestational stages in many states. In addition to bans on abortion altogether, many states impose other limitations on abortion that are not medically indicated, including waiting periods, ultrasound requirements, and parental notification and consent requirements. These restrictions typically delay receipt of services and can increase costs associated with abortion care. As use of medication abortion has risen, some have tried to cast false doubt about the safety of the medications, despite the extensive body of research on the drug’s safety. There are multiple efforts to restrict use of the drug nationally, and two states have classified mifepristone as a controlled substance to limit its availability.

Obtaining an abortion can be costly, with median costs exceeding $500 in out-of-pocket expenses for patients who self-pay. On average, the costs are higher for abortions in the second trimester than in the first trimester. People may have to travel if abortions are prohibited or not available in their area, adding costs related to travel and lodging. Given abortion bans and Hyde Amendment restrictions on payment for abortions under Medicaid and state restrictions on insurance coverage of abortion services, many people pay for abortion services out of pocket. Some people are able to receive assistance from local abortion funds if they need financial support to obtain abortion services, particularly if they have to travel out of state or have low incomes and cannot afford the costs of the abortion. For some, however, the costs of abortion services and travel will put the service out of reach and force them to have a birth that is not desired or is a risk to their health or life.

Insurance coverage for abortion services is heavily restricted in some state-regulated private insurance plans and public programs, like Medicaid and Medicare. Private insurance covers most women of reproductive age, and states can choose whether abortion coverage is included or excluded in private plans that are not self-insured. Prior to the Dobbs ruling, about half of the states had enacted private plan restrictions and banned abortion coverage from ACA Marketplace plans. Since the Dobbs ruling, some of these states have also banned the provision of abortion services altogether. However, 12 states have enacted laws that require private plans to cover abortion, typically without cost-sharing.

The Hyde Amendment has banned the use of federal funds for abortion unless the pregnancy is a result of rape, incest, or it endangers the woman’s life. States may use non-federal state-only funds to pay for abortions under other circumstances for women covered by Medicaid, which 20 states currently do. However, more than half (56%) of women covered by Medicaid live in states where they have no coverage for abortion, unless they qualify for an exception.

The impact of the Dobbs decision goes far beyond abortion care. It has also affected the provision of related health care services, including management of miscarriages and pregnancy-related emergencies, treatments for cancer and other chronic illnesses, contraceptive options, and much more. Women with low incomes, women of color, sexual/gender minorities, and other pregnant people have been disproportionately affected by the sweeping impacts of this ruling, as they are less likely to have the resources to travel potentially long distances to seek care.

Since the Dobbs ruling, there has been a constant stream of legal challenges, with a plethora of cases that seek to challenge abortion bans as well as block access to abortion medication or services. The Supreme Court has considered two abortion related cases—one case involving the FDA’s approved conditions for using and dispensing mifepristone, one of the drugs used for medication abortion, as well as a case about potential conflict between state-level abortion bans and Emergency Medical Treatment and Labor Act (EMTALA), the federal law that requires hospitals to provide care to stabilize patients experiencing medical emergencies, including emergency abortions that must be performed to save the life or preserve the health of the pregnant patient. Several other cases about abortion access are pending in lower courts.

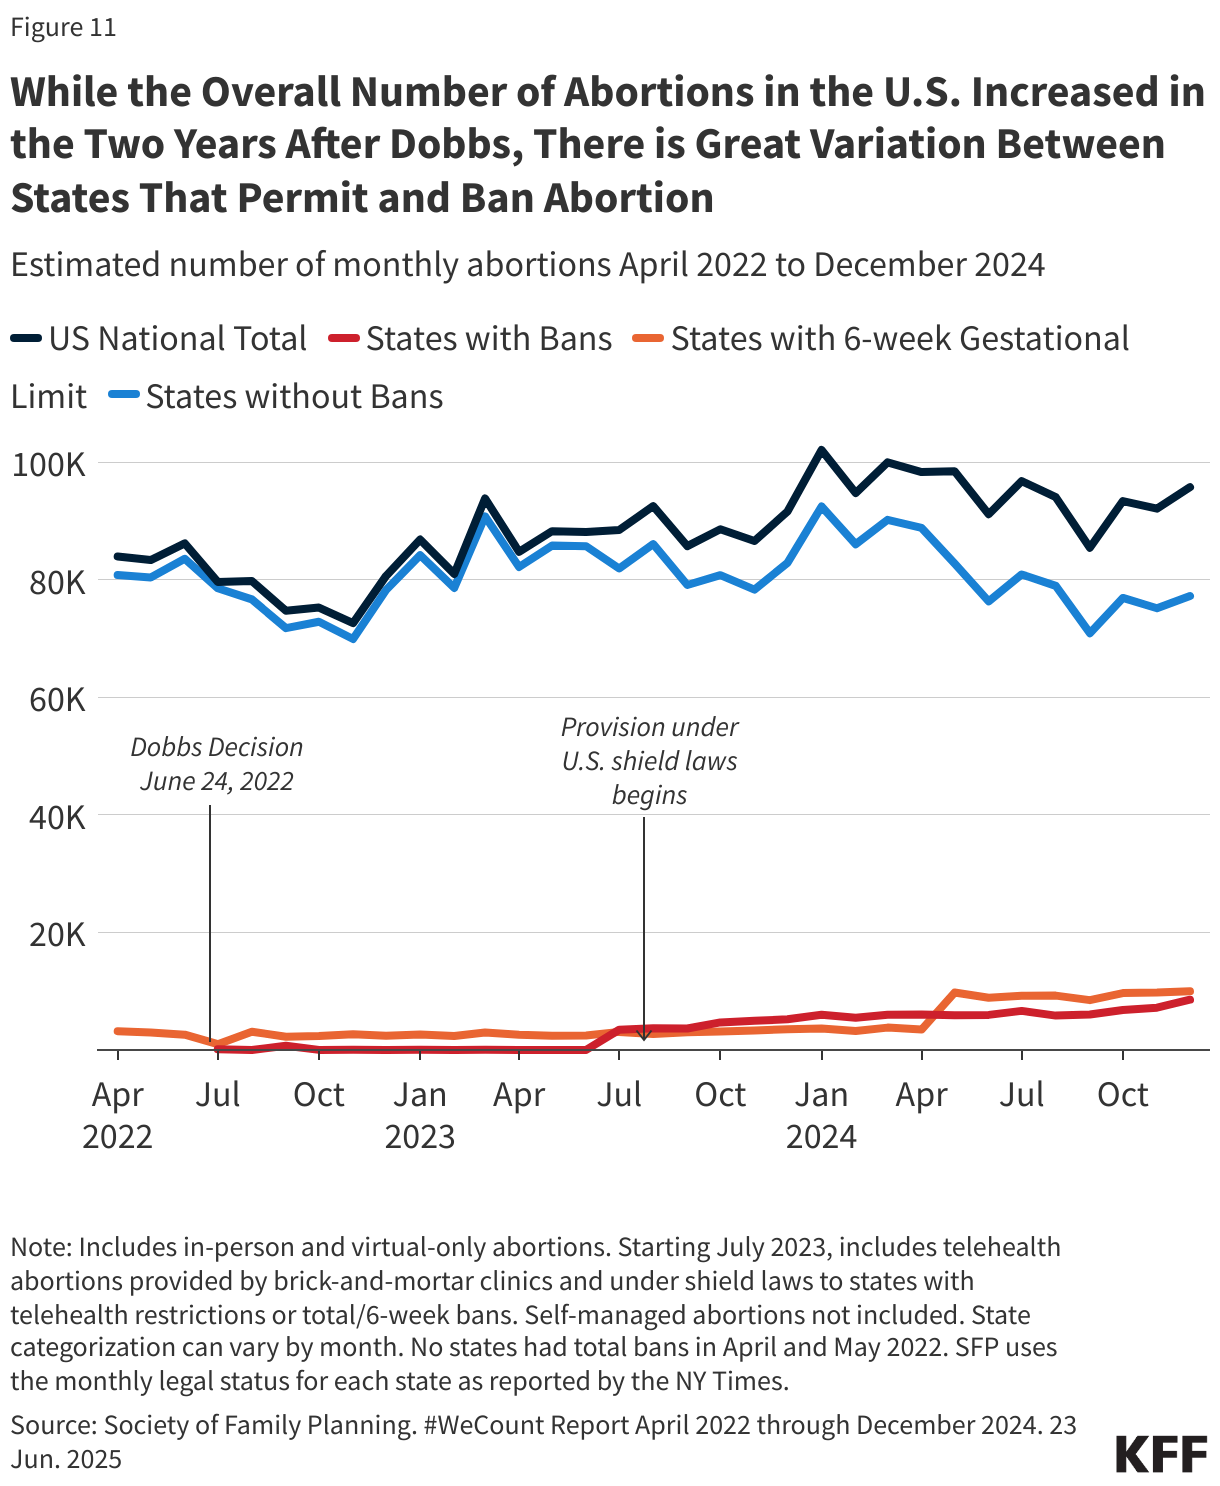
Paradoxically, the most recent data show that the abortion volume in the U.S. slightly increased overall in the two years following the Dobbs ruling (Figure 11). In 2024, the national abortion volume averaged 95,200 abortions per month, higher than the monthly averages in 2023 and before the Dobbs decision. This overall increase can be largely attributed to broader availability of lower cost medication abortions through telehealth, virtual clinics, brick and mortar clinics, and shield laws, where clinicians in legal states mail pills to individuals residing in states with bans and restrictions. Additionally, in several states without bans, there has been increased interstate travel for abortion access, expanded capacity to see patients, increased measures to protect abortion rights and improve coverage of abortion care.

However, the small upswing nationally obscures the massive declines in abortion access to in-state providers in states with bans and restrictions as well as the hardships that many pregnant people experience in accessing abortion care. Additionally, there are month-to-month variations in all states, and changes in policy can cause larger shifts. For example, in May 2024 Florida implemented a ban on abortions after six weeks of gestation (previously permitted up to 15 weeks), and subsequently there was a noticeable decline in abortions in the state and nationally.

While the Overall Number of Abortions in the U.S. Increased in the Two Years After Dobbs, There is Great Variation Between States That Permit and Ban Abortion (Line chart)

Contraception

Contraceptive care is an important component of overall health care for many women and people capable of becoming pregnant. Federal and state policies shape access to and the availability of contraceptive care, but factors such as provider characteristics, as well as individual preferences and experiences also impact contraceptive choices and use. For most people, private insurance coverage and Medicaid greatly reduce or eliminate financial barriers to contraceptive care. However, access is still limited in many parts of the U.S. with more than 19 million women living in contraceptive deserts where they may not have access to a health center offering the full range of contraceptive methods. There have been more efforts to broaden contraceptive availability outside of traditional clinical settings, including through commercial apps that use telehealth platforms, state efforts to allow pharmacists to prescribe birth control, and, most recently, over-the-counter (OTC) access to contraceptives without a traditional prescription.

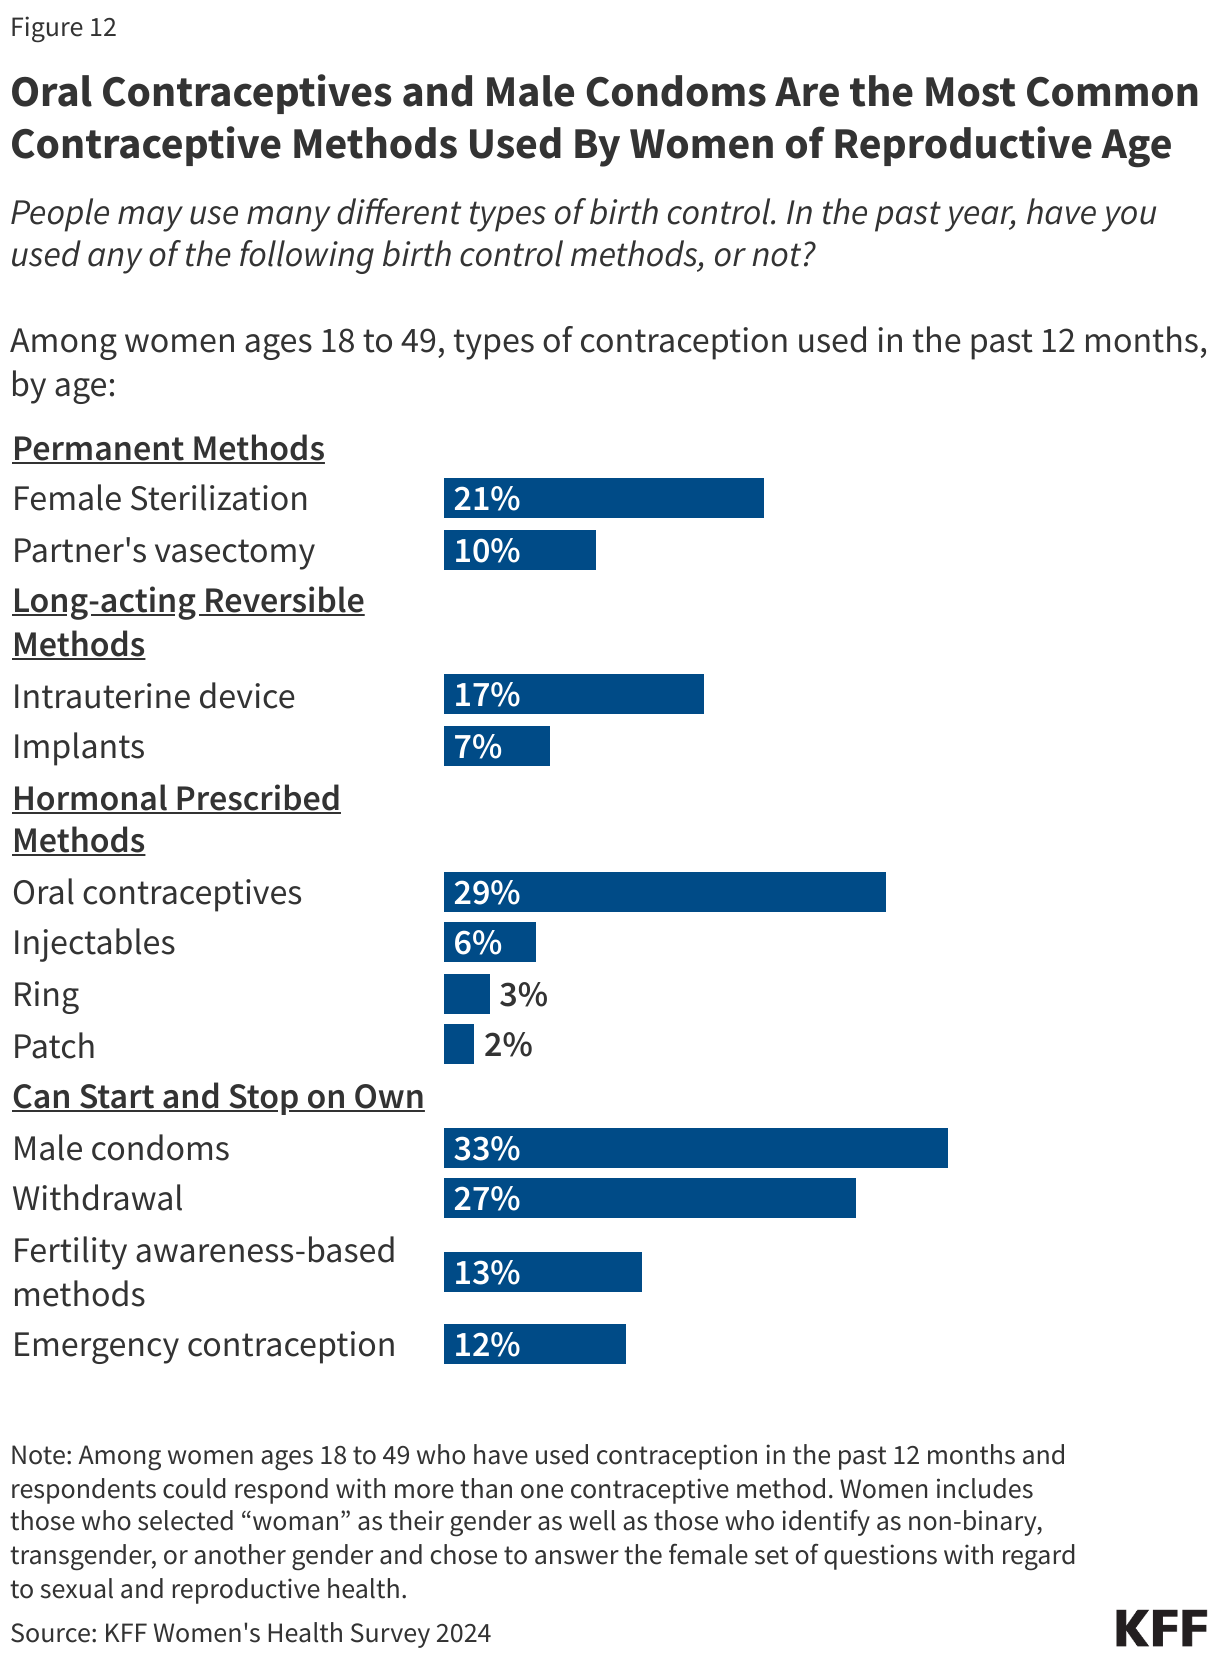
The importance and impact of contraceptives in women’s lives are unquestionable. The 2024 KFF Women’s Health Survey highlighted that the majority of women ages 18 to 49 (82%) have used contraception in the past 12 months,  most commonly oral contraceptives and male condoms (Figure 12). The types of contraception women use shift over the course of their reproductive years. Forty-four percent of women ages 18 to 25 report having used oral contraceptives in the past 12 months compared to 19% of women ages 36 to 49. Conversely, higher shares of older women say they have had a sterilization procedure compared to younger women.

Oral Contraceptives and Male Condoms Are the Most Common Contraceptive Methods Used By Women of Reproductive Age (Bar Chart)

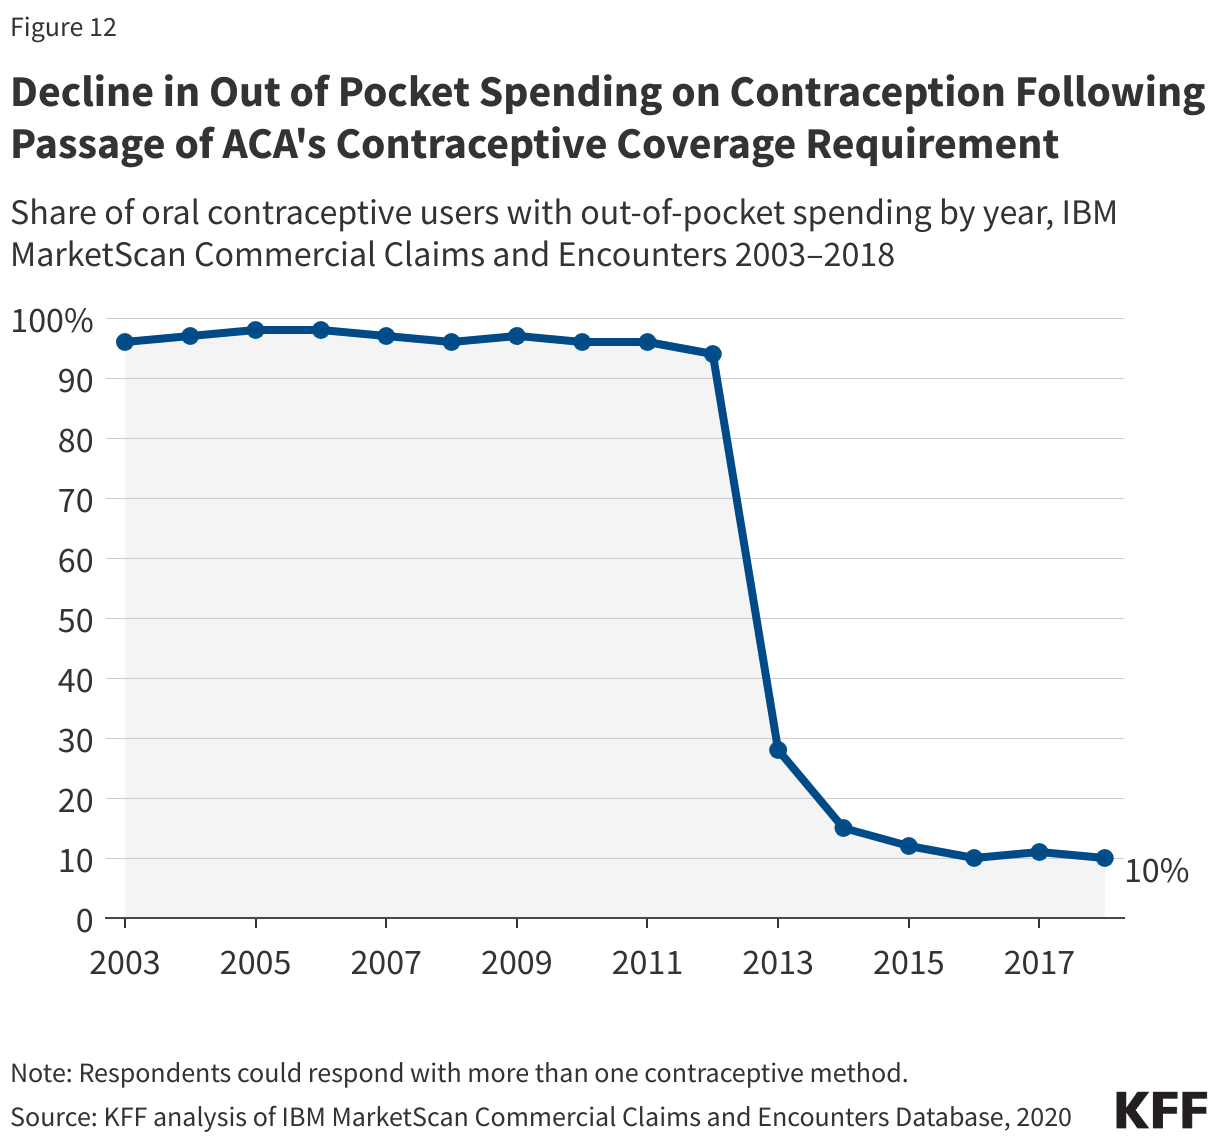
The ACA requires that most private plans cover contraceptive services for females without cost-sharing – this includes patient education and counseling and FDA-approved methods of contraception with a prescription. This provision has dramatically reduced cost-sharing for contraception among females with private insurance plans, though some privately insured females who are eligible for no-cost coverage are still paying some of the cost of their contraceptives (Figure 13). Reasons include someone using a brand-name contraceptive that is not in the plan’s formulary or consumers unaware of or not offered a generic alternative.

Decline in Out of Pocket Spending on Contraception Following Passage of ACA's Contraceptive Coverage Requirement (Line chart)

Despite its far-reaching impact, the ACA’s requirement for contraceptive coverage has been challenged in the courts on multiple occasions, with three cases reaching the Supreme Court. The earlier cases, Burwell v. Hobby Lobby (2014) and Zubik v. Burwell (2016), challenged the Obama Administration's regulations implementing the contraceptive coverage requirement, contending that the requirement violated some employers’ religious rights. The most recent cases, Little Sisters of the Poor v. Pennsylvania (2020) and Trump v. Pennsylvania (2020), involved regulations issued by the Trump Administration, which currently exempt employers with religious objections from providing contraceptive coverage to their employees.

For people with lower incomes, the Medicaid program is the primary funding source for contraceptives. The federal Medicaid statute establishes minimum standards, and, for decades, has classified family planning as a mandatory benefit category that all state programs must cover. States may not charge any out-of-pocket costs for family planning services and must allow beneficiaries to see any Medicaid provider within their state for family planning care. Many states also have programs that provide Medicaid coverage just for family planning services to people who have lower incomes but do not qualify for full Medicaid benefits.

Additionally, the federal Title X family planning program, administered by the HHS Office of Population Affairs (OPA), is the only federal program specifically dedicated to supporting the delivery of family planning care for individuals who are uninsured and have lower incomes. The program provides funding to more than 4,000 health clinics, public health departments, and nonprofit agencies across the country to deliver contraceptives and other family planning services to individuals with low incomes. Title X-funded providers must follow the program’s requirements, which include offering a broad range of family planning methods for low or no cost and ensuring confidentiality for adolescents. Federal rules also require that participating clinics offer their patients non-directive pregnancy option counseling that includes abortion, adoption, and prenatal referral for those who seek those services. Over the last decade, there have been major changes to the Title X program based on shifting administrations’ priorities. During the first Trump Administration, the regulations were revised to disqualify clinics that had co-located abortion services and provided abortion referrals. Over 1,000 clinics were no longer eligible for Title X funds. The Biden Administration reversed the Trump Administration regulations and funding was restored to many of these clinics. The second Trump administration has been withholding funds from some of the program’s grantees, including all 9 Planned Parenthood grantees. Hundreds of Title X Clinics are affected, and some have reported that they are closing as a result . In addition, the President’s proposed budget calls for the elimination of the Title X program.  

While there have been numerous over-the-counter contraceptive methods available (e.g. condoms, spermicides), in July 2023, the Food and Drug Administration (FDA) approved the first over-the-counter daily oral contraceptive pill, known as Opill. FDA’s approval of Opill makes it the most effective form of contraception available OTC intended for regular use. Private insurers and Medicaid generally require a prescription to cover OTC products, so even though Opill and other OTC products are available without needing a prescription from a clinician, coverage without a prescription will be limited without federal or state action.

Mental Health

Mental health has emerged as a rapidly growing concern in recent years, with 90% of Americans saying there is a mental health crisis in a 2023 KFF-CNN poll. Women experience several mental health conditions such as anxiety, depression, and eating disorders more frequently than men, and some also experience mental health disorders that are unique to women, such as perinatal depression (including prenatal and postpartum depression) and premenstrual dysphoric disorders that may occur when hormone levels change.

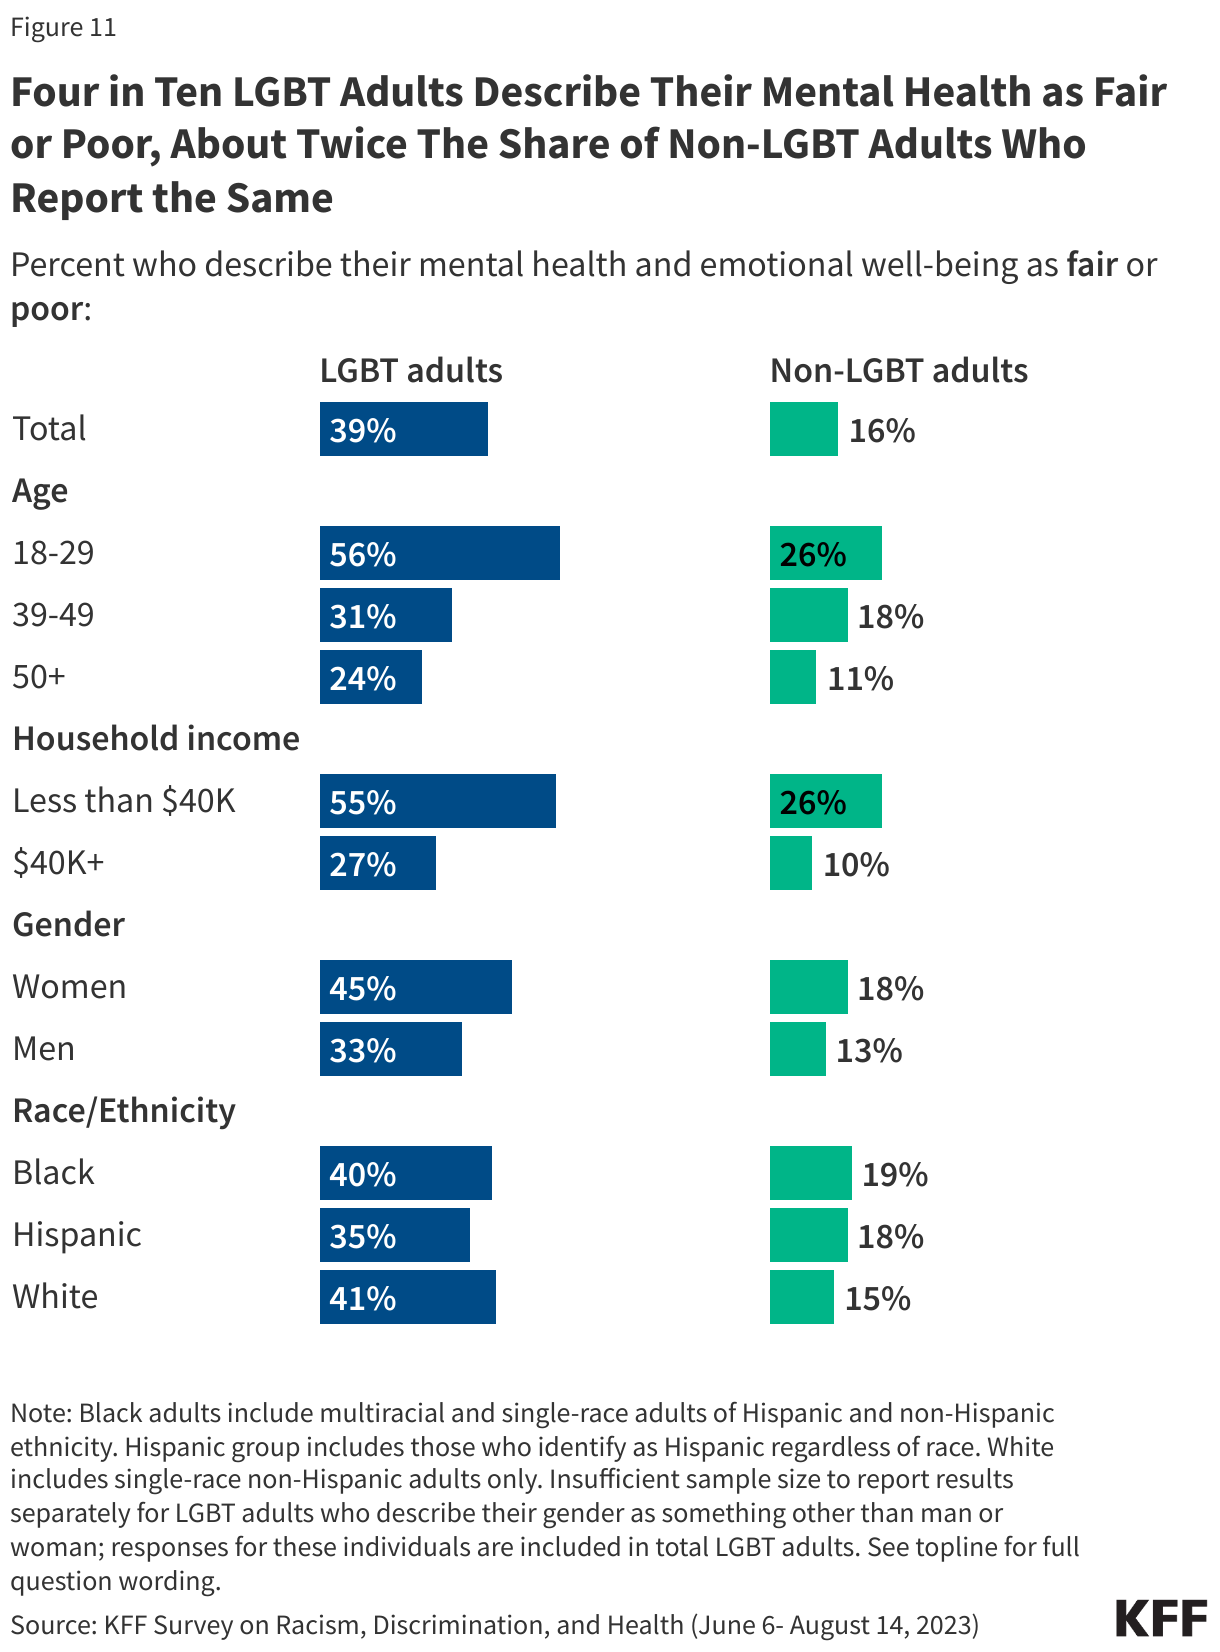
A KFF survey found that in 2024, a higher share of women (28%) than men (23%) describe their mental health as fair or poor (data not shown). Higher rates of women 18 to 25 (36%), those with incomes below 200% of the FPL (38%), those who identify as LGBT+ (45%), and those who identify as having a mental health-related disability (73%) report fair or poor emotional wellbeing. Roughly three in the ten women (29%) say they received mental health services from a mental health professional, however many experience challenges while trying to find care. Among women who received mental health care in the past 12 months, more than half (55%) say they experienced a barrier during their care seeking journey, including trouble finding a provider that was accepting new patients (25%), trouble finding a provider that accepted their  (21%), and trouble scheduling an appointment in a reasonable amount of time (24%).

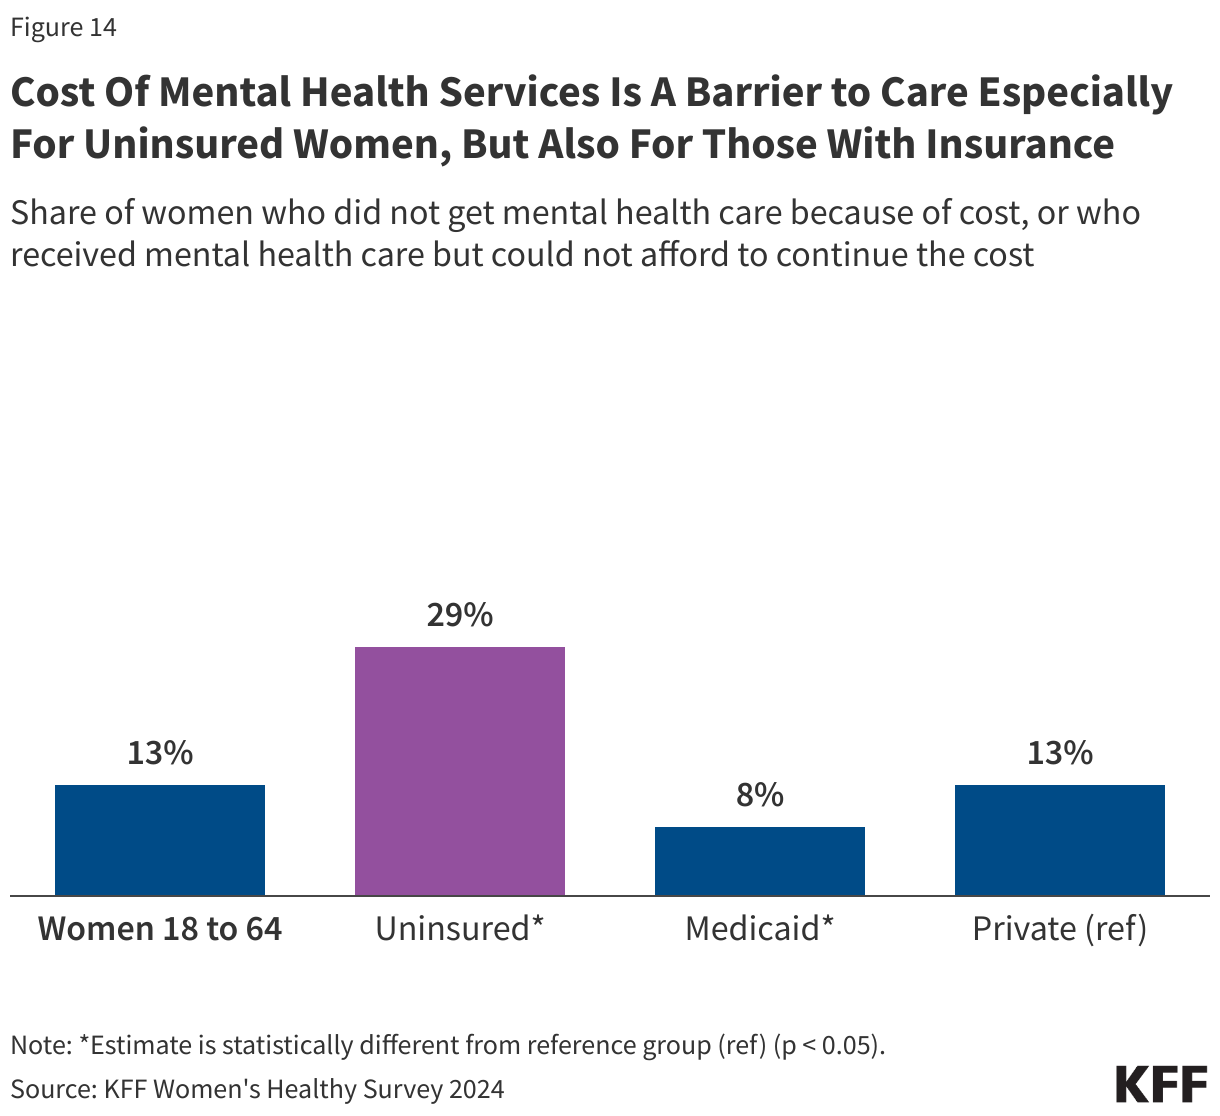
Cost is a commonly reported barrier to mental health care. More than one in ten women 18 to 64 (13%) say they did not get mental health care or could not continue to afford the mental health care they were receiving because of cost (Figure 14). Insurance networks can be very narrow for mental health care, and a significant portion of mental health clinicians do not participate in insurance networks. These findings on cost barriers underscore the ongoing challenges with affordable mental health care, especially among women who are uninsured, but even for those with coverage.

Cost Of Mental Health Services Is A Barrier to Care Especially For Uninsured Women, But Also For Those With Insurance (Column Chart)

The ongoing opioid epidemic is a commonly cited stressor that has exacerbated long-standing mental health issues and prompted growing demand for mental health services in the past several years. Women face unique gender and sex-related differences when it comes to substance use, including greater physical, psychological, and social harms associated with drug use. Use of certain substances in women has been linked to increased rates of depression and anxiety disorders. Studies have also shown that women who use substances are at risk for issues related to pregnancy, fertility, breastfeeding, menstrual cycle, and more. All of these factors also shape the availability of treatment and services accessible to women.

Intimate Partner Violence Against Women

Intimate partner violence (IPV), defined as sexual violence, stalking, physical violence, and psychological aggression perpetrated by a current or former intimate partner, affects nearly a third of all Americans at some point in their lives. Although IPV affects men and women of all ages, women experience IPV at higher rates. Rates are higher among some groups of women, particularly those who are young, Black, American Indian or Alaska Native, and LGBTQ. People who experience IPV are more likely to experience a range of health problems such as chronic pain, cardiovascular problems, and neurological problems. Both the CDC and U.S. Preventive Services Task Force (USPSTF) have identified IPV as a significant public health issue in the U.S.

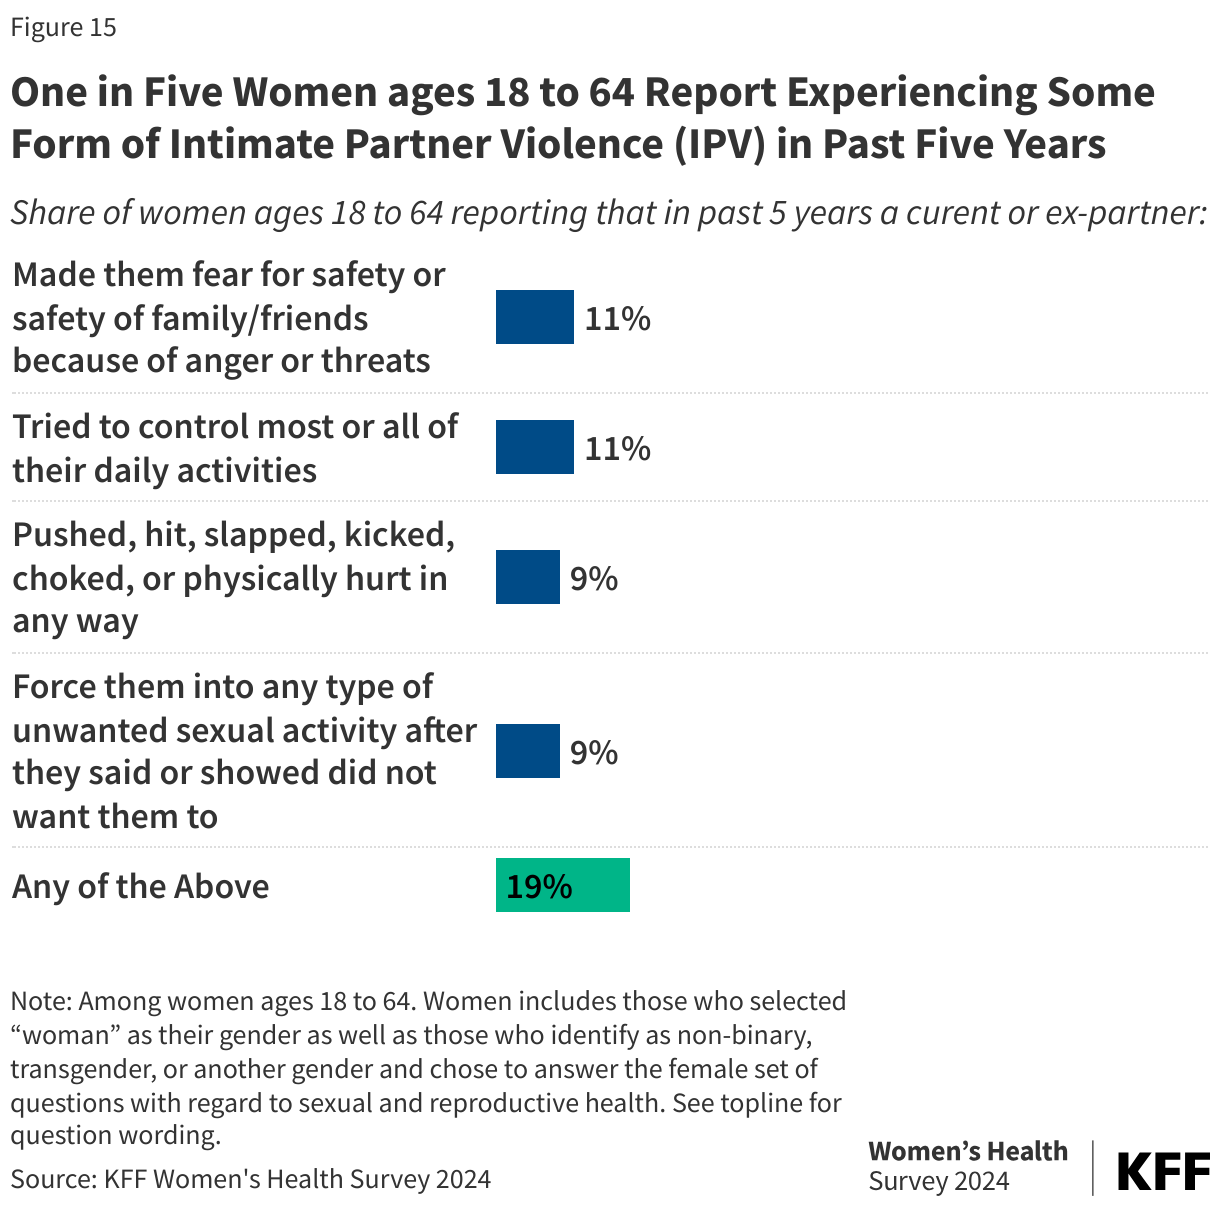
It is difficult to quantify the number of people who experience IPV, as many cases are not reported. Some studies have estimated 6.5 million women in the U.S. experience sexual violence, physical violence, or stalking by an intimate partner in a single year. According to the 2024 KFF Women’s Health Survey, one in five women report experiencing some form of IPV in the past five years (19%), including instances where a current or former partner made them fear for their safety (11%), tried to control most of all of their daily activities (11%), physically hurt them (9%), or forced them into any type of unwanted sexual activity (9%) (Figure 15).

One in Five Women ages 18 to 64 Report Experiencing Some Form of Intimate Partner Violence (IPV) in Past Five Years (Bar Chart)

Several federal programs and laws fund health care services and supports to survivors of IPV. The Violence Against Women Act (VAWA) has a broad scope, covering domestic violence, sexual harassment, stalking, and sexual assault. VAWA provides grants to states, local governments, and other organizations to establish their own violence-related programs and protocols. While some of the focus of VAWA and other public policies is prosecution of those who commit violence, provisions in VAWA also address health care coverage and costs for people who have experienced IPV.

It is well recognized that the health care system can serve as a site of IPV screening and support, and some professional medical organizations recommend that clinicians screen women for IPV. Under the ACA, IPV screening is considered a preventive service as screening is recommended by the USPSTF and Health Resources and Services Administration (HRSA) preventive services for women. When health care providers routinely screen patients for IPV, it helps identify cases and connect survivors to resources and supports. However, this can be challenging as a KFF survey of OBGYNs found that many clinicians say they do not have sufficient resources within their practices to provide follow-up services when cases of IPV are identified. Connections to community-based services are particularly important for clinicians to be able to care for patients who disclose IPV.

Future Outlook

Copy link to Future Outlook

Women’s health has become one of the most politicized issues in society and health care. The overturning of Roe v. Wade in 2022 marked a seismic change in an important aspect of women’s health care that has implications for all pregnancy-related care and women’s economic future and well-being. The high and rising rates of maternal mortality and morbidity in the U.S. and the persistent gaps in mortality rates experienced by women of color highlight the need to address the roles that poverty, racism, and discrimination play in women’s health.

The Trump Administration has proposed major changes that could affect many recent gains in women’s health care. Within the first few months of taking office, the Administration has sought to define sex as “an individual’s immutable biological classification as either male or female,” which is not supported by science, proposed to eliminate the Office of Population Affairs (OPA), and raised doubts about the safety of mifepristone without scientific basis, to name a few. Significant cuts to several HHS agencies, including HRSA, CDC, FDA, and NIH, have reduced support for women’s health programs and research across the country, with more likely to come. The Administration opposes federal programs related to racial equity, which is integrally connected with most women’s health issues such as maternal health. In addition, the federal budget reconciliation law that was enacted in 2025 made major cuts to the Medicaid program and the ACA, which will affect access to affordable coverage and care for women and families with low incomes. Over the next several years, these cuts in federal spending are projected to lead to a steep rise in people who are uninsured and reduced funding for states and health care providers, including those that care for women with lower incomes. At the same time, the Administration is calling for an increase in births while cutting programs that support families, such as food stamps and HeadStart. While much of the focus in the years will be on the effects of these cuts to federal health spending and programs, some of the key challenges that remain to be addressed in women’s health include:

  • How to address and eliminate the persistent inequities in health coverage and outcomes experienced by women of color?
  • How to build a delivery system and develop coverage policies that is responsive to the reproductive and sexual health needs of women and other gender minorities to promote optimal health outcomes?
  • How to maintain a strong safety-net that offers high quality sexual and reproductive health services, with rising health care costs, a potential increase in uninsured rates, and a decrease in public funds?
  • How to shape policies that protect women with low incomes from experiencing financial barriers to care
  • Identifying and implementing policies that improve maternal health outcomes and also eliminate the structural and systemic barriers to care
  • Providing access to comprehensive care to pregnant people who live in areas where abortion is unavailable due to state-level bans and restrictions
  • How to provide care to women dealing with issues that are heavily stigmatized and marginalized, such as intimate partner violence and mental health challenges.

Resources

Copy link to Resources

Citation

Copy link to Citation

Ranji, U., Diep, K., Gomez, I., Sobel, L., & Salganicoff, A., Health Policy Issues in Women's Health. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-health-policy-issues-in-womens-health/ (date accessed).

Race, Inequality, and Health

Table of Contents

Introduction

Copy link to Introduction

Health and health care disparities refer to preventable differences in health and health care among groups that stem from broader social and economic factors. Despite the recognition of disparities for decades and overall improvements in population health over time, many disparities persist, and in some cases, have widened over time. Disparities limit the overall health of the nation and result in unnecessary costs. This chapter provides an overview of what health and health care disparities are, the factors that drive them, the status of racial and ethnic health and health care disparities today, how recent federal actions may impact disparities, and future considerations. The information and data included in this chapter are current as of July 2025.

In the wake of the COVID-19 pandemic and racial reckoning following the murders of George Floyd and others, the federal government as well as many states and private entities increased efforts focused on addressing health disparities. Since taking office, the Trump administration has taken a range of actions to eliminate federal diversity and disparities-related initiatives, restructured and eliminated federal staff and offices that played key roles in identifying and addressing disparities, and implemented policies focused on restricting immigration and increasing interior enforcement to support mass deportation of immigrants. Moreover, the 2025 federal budget reconciliation law makes large cutbacks to federal spending for Medicaid and the Affordable Care Act’s (ACA’s) provisions. These actions will likely lead to widening disparities in health and health care going forward.

What are Health and Health Care Disparities?

Copy link to What are Health and Health Care Disparities?

Health and health care disparities refer to preventable differences in health and health care among groups that stem from broader social and economic factors. There are multiple definitions of health disparities. The Centers for Disease Control and Prevention (CDC) defines health disparities as “preventable differences that populations experience in the burden of disease, injury, violence, or opportunities.” A health care disparity typically refers to differences between groups in health insurance coverage, affordability, access to and use of care, and quality of care. The terms “health inequality” and “inequity” also are used to describe differences that stem from systemic and unjust or inequitable social and economic policies. Racism, which the CDC previously defined as a system that includes structural, institutional, interpersonal, and internalized racism that assigns value and determine opportunities based on the way people look or the color of their skin, results in conditions that unfairly advantage some and disadvantage others. Racism and discrimination at all levels, intentional or not, contribute to differences in experiences across many aspects of everyday life as well as in health care settings, which can negatively impact people’s health and well-being.

Reflecting the intersectional nature of people’s identities, some individuals experience disparities across multiple dimensions beyond race and ethnicity such as citizenship, sexual orientation and gender identity, and disability status.  Disparities also occur within subgroups of broader racial and ethnic groups, such as gender, ethnic identity, immigration status, and English proficiency. For example, a KFF survey shows that Black women report more pervasive negative experiences in health care settings compared to other groups. These groups are not mutually exclusive and often intersect in meaningful ways.  The Healthcare Research and Quality Act of 1999, which established an Office of Priority Populations within the Agency for Healthcare Research and Quality (AHRQ) identifies designated priority populations, including “low-income populations, racial/ethnic minorities, maternal health, women, children/adolescents, elderly, and individuals with special health care needs.” The National Institute on Minority Health and Health Disparities, established under the Minority Health and Health Disparities Research and Education Act also has designated populations with health disparities, including “racial and/or ethnic minority populations, low socioeconomic status, underserved rural populations, people with disabilities, and sexual minority groups.”

Health equity generally refers to individuals achieving their highest level of health through the elimination of disparities in health and health care. The CDC describes health equity as when everyone has a fair and just opportunity to be as healthy as possible. The World Health Organization (WHO) states that “health equity is achieved when everyone can attain their full potential for health and well-being.” The WHO defines equity as the absence of unfair and avoidable differences among groups, regardless of their identity, where they live, and other social and economic factors. The terms health equity and equality both refer to efforts to achieve better health outcomes and access to health care services for all groups. While health equality refers to providing all people with the same resources and opportunities, it does not account for people’s different underlying needs or circumstances that may affect their ability to achieve optimal health outcomes and health care access.

What Factors Drive Racial and Ethnic Health Disparities?

Copy link to What Factors Drive Racial and Ethnic Health Disparities?

The U.S. has a long history of policies and events that have resulted in stark differences in access to resources, opportunities, and power that contribute to racial and ethnic disparities in health today. Dating back to slavery and colonization of the Americas, people of color have been subject to abuse and mistreatment, including medical exploitation and experimentation, family separation, and efforts to eliminate cultural practices and languages. Historical discriminatory policies, such as redlining, have lasting effects today, leading to residential segregation of Black and Hispanic people into urban neighborhoods with more limited resources and increased health risks, including climate-related risks. Within medicine, disproven beliefs about biological differences by race persist today and have led to race permeating clinical decision making and treatment in multiple ways, including through providers’ attitudes and implicit biases, disease stereotyping and clinical nomenclature, and its use in clinical algorithms, tools, and treatment guidelines. Similarly, historical anti-immigrant policies have excluded and discriminated against certain groups, contributing to “othering” and “perpetual foreigner” stereotypes, particularly among Asian immigrants, with a resurgence in anti-Asian rhetoric amid the COVID-19 pandemic. Policies, such as the 1996 Welfare Reform Law, have restricted access to public assistance programs, including health coverage, contributing to persistent disparities in health coverage and care for immigrants today, who are disproportionately Hispanic or Asian.

Underlying inequities in social and economic factors that reflect historical and contemporary policies drive racial and ethnic disparities in health (Figure 1). Though health care is essential to health, studies suggest that social and economic factors, often referred to as  social determinants of health, are the primary drivers of health outcomes. These include factors such as access to housing, food, and economic and educational opportunities. Hispanic, Black, AIAN, and NHPI people fare worse compared to White people across many social and economic factors. Experiences for Asian people are mixed, although some subgroups of Asian people fare worse compared to White people. Asian immigrants face certain additional challenges.

Experiences with unfair treatment and discrimination negatively impact health and well-being. Despite growing calls to address racism in the wake of the COVID-19 pandemic and the accompanying racial reckoning, many adults continue to experience unfair treatment and discrimination in their daily lives and in health care settings. A 2023 KFF survey finds that at least half of AIAN (58%), Black (54%), Hispanic adults (50%), and about 4 in 10 Asian adults (42%) say they experienced at least one type of discrimination in daily life in the past year. These experiences include receiving poorer service than others at restaurants or stores; people acting as if they are afraid of them or as if they aren’t smart; being threatened or harassed; or being criticized for speaking a language other than English. Consistent with other research, which shows that racism has negative effects on mental health and results in certain negative physical health outcomes, among those with discrimination experiences, 4 in 10 (40%) say they “always” or “often” felt anxious in the past year, compared to 14% of adults who rarely or never experience such discrimination (Figure 2). Similarly, those with experiences of discrimination in their daily life are more than three times as likely as others to say they always or often felt lonely (26% vs. 7%) or depressed (25% vs. 7%) in the past year.

Adults Who Experience Discrimination Are More Likely Than Those Who Do Not To Report Feeling Anxious, Lonely, Or Depressed

Racism and discrimination also negatively affect people’s health care experiences. KFF survey data also show that Black, Hispanic, AIAN, and Asian adults report higher levels of unfair treatment when seeking health care than their White counterparts and are more likely to report having certain negative experiences with a health care provider because of their race and ethnicity (Figure 3). About a quarter of adults who experienced unfair treatment, a negative experience with a provider, or a language access challenge say it led to worse health, being less likely to seek care, and/or switching providers. Similarly, as of 2023, one in four (25%) immigrant adults said that they were treated unfairly by a health care provider in the U.S., including nearly four in ten (38%) Black immigrant adults.

About One In Five Black Adults And One In Ten Hispanic, Asian, And AIAN Adults Report Unfair Treatment By A Health Care Provider Due To Race Or Ethnicity

Why Is It Important to Address Disparities?

Copy link to Why Is It Important to Address Disparities?

Addressing disparities in health and health care is important not only from an equity standpoint but also for improving the nation's overall health and economic prosperity. Racial and ethnic health and health care disparities result in higher rates of illness and death across a wide range of health conditions, limiting the overall health of the nation. Research further finds that health disparities are costly, resulting in excess medical care costs and lost productivity, as well as additional economic losses due to premature deaths each year.

It is increasingly important to address health disparities as the population becomes more diverse and stark income inequalities persist (Figure 4). The population has become increasingly racially diverse, reflecting shifting immigration patterns, a growing multiracial population, as well as adjustments to how the U.S. Census Bureau measures race and ethnicity. The U.S. Census Bureau projects that people of color will account for over half (52%) of the population in 2050, with the largest growth occurring among people who identify as Asian or Hispanic. Income inequality within the U.S. has also widened over time. As of 2023, the top 10% of households in the U.S. had incomes above $216,000 compared with incomes at or below $17,100 among the lowest 10% of households.

People Of Color Are Projected To Make Up Over Half Of The U.S. Population As Of 2050

What Is the Status of Racial and Ethnic Disparities in Health Today?

Copy link to What Is the Status of Racial and Ethnic Disparities in Health Today?

Major recognition of health disparities began nearly four decades ago. In 1985, the Report of the Secretary’s Task Force on Black and Minority Health (commonly known as the Heckler Report) documented persistent health disparities that accounted for 60,000 excess deaths each year and synthesized ways to advance health equity. The Heckler Report led to the creation of the Office of Minority Health within the Department of Health and Human Services (HHS) (which was reportedly shut down by the Trump administration as part of the HHS staff restructuring and reductions) and influenced federal recognition of and investment in many aspects of health equity. In 2003, the Institute of Medicine’s Unequal Treatment: Confronting Racial and Ethnic Disparities in Health Care report was issued, which identified systemic racism as a major cause of health disparities in the United States.

Despite the recognition and documentation of disparities for decades and overall improvements in population health over time, many disparities persist, and in some cases, have widened over time .Analysis across a broad range of health measures finds that Black and AIAN people fare worse than their White counterparts across half or more of these measures. Data for Hispanic people are more mixed relative to White people, with them faring better on some measures but worse on others. In the aggregate, Asian people fare the same or better than White people on many measures of health, although this finding masks disparities among subgroups of the population. Data gaps limit the ability to examine disparities among NHPI people; where data are available, they point to disparities, particularly for certain subgroups of this population. Overall, Black, Hispanic, and AIAN people fare worse compared to White people across many measures of health outcomes including:

  • AIAN and Black people had a shorter life expectancy at birth compared to White people based on provisional data from 2022. Life expectancy for Black people was about five years shorter than White people (72.8 vs. 77.5), and nearly ten years shorter for AIAN people (67.9).
  • AIAN, Hispanic, and Black people experienced larger declines in life expectancy than White people between 2019 and 2021, largely reflecting an increase in excess deaths due to COVID-19.
  • NHPI people had the highest age adjusted mortality rates for diabetes among all racial and ethnic groups at 49.6 per 100,000 deaths. The age-adjusted mortality rates for diabetes for AIAN (41.5 per 100,000) and Black people (39.1 per 100,000) were about twice as high as the rate for White people (19.8 per 100,000); Hispanic people (26.5 per 100,000) also had a higher diabetes death rate compared to White people in 2023. Although Black people did not have higher cancer incidence rates than White people overall and across most types of cancer, they had the highest overall cancer-related mortality rate as of 2022. Black people (165 per 100,000 deaths) were more likely to die from cancer than White people (148.4 per 100,000), and NHPI people had a slightly lower overall cancer-related mortality rate (141.4) to White people in 2022.
  • Black infants were more than two times as likely to die as White infants (10.9 vs. 4.5 per 1,000 live births) as of 2023. AIAN infants (9.1 per 1,000) were roughly twice as likely to die as White infants (Figure 5). Hispanic infants (4.9 per 1,000) also had a slightly higher mortality rate than White infants in 2023.
  • AIAN (118.7 per 100,000), NHPI (111.7 per 100,000), and Black (69.3 per 100,000) women also had the highest rates of pregnancy-related mortality in 2021
Black, AIAN, and NHPI People Have Higher Infant Mortality Rates Compared To Other Groups  

There are also ongoing racial and ethnic disparities in health coverage and access to care.  Despite large gains in coverage across groups since the ACA coverage expansions were implemented in 2014, as of 2022, nonelderly AIAN, Hispanic, Black, and NHPI people were more likely to be uninsured compared to their White counterparts (Figure 6). There are also large coverage disparities by immigration status, with a 2023 KFF/LA Times Survey of Immigrants showing that about one in five (18%) lawfully present immigrant adults and half (50%) of likely undocumented immigrant adults reported being uninsured as compared to less than one in ten citizens. In addition, Hispanic, Black, Asian, AIAN, and NHPI adults are more likely than White adults to report not having a personal health care provider, and Hispanic, Black, AIAN, and NHPI adults are more likely than White adults to report not seeing a doctor in the past 12 months because of cost.

Despite Large Gains In Coverage, Racial And Ethnic Disparities Remain

How Could Recent Federal Actions Impact Disparities?

Copy link to How Could Recent Federal Actions Impact Disparities?

In the wake of the COVID-19 pandemic and racial reckoning following the murders of George Floyd and others, the federal government as well as many states and private entities increased efforts focused on addressing health disparities. This increased focus led to the development of programs and initiatives focused on mitigating disparities, including efforts to address disparities in maternal and infant health, cancer, and chronic disease, as well as other efforts, such as increasing diversity in clinical trials for development of new drugs and devices. Research efforts also increased to understand disparities, the factors driving them, and effective interventions to mitigate them.

The Biden administration issued a series of executive orders and other efforts to advance health equity.  These included orders that outlined equity as a priority for the federal government, equity as a central part of the pandemic response and recovery efforts, and also directed federal agencies to develop Equity Action Plans. HHS’ equity action plan outlined a series of strategies that included efforts to improve access and address barriers to quality and affordable health care; prioritize behavioral health for underserved populations; and improve maternal health outcomes for rural, Tribal, and underserved racial and ethnic groups. HHS also enacted its climate action plan, including establishing the Office of Climate Change and Health Equity to address the impacts of climate change on health outcomes and health equity.  The administration released a Blueprint for Addressing the Maternal Health Crisis, a whole government approach to combatting maternal mortality and morbidity with a focus on reducing disparities in maternal health outcomes and improving overall pregnancy, birth, and postpartum outcomes. Federal efforts were also made to increase the availability of disaggregated data for smaller population groups, including AIAN and NHPI people, to understand and address the health and heath care disparities they face. During his term, President Biden reversed public charge regulations from the Trump administration’s first term to reduce fears about participating in programs, including Medicaid and the Children’s Health Insurance Program.

As one of his first actions in office, President Trump signed executive orders revoking federal diversity, equity, inclusion, and accessibility (DEIA) related programs and actions in the federal government and among federal contractors and grantees.  In implementing President Trump’s executive orders, the administration has taken significantly broader actions beyond eliminating DEI programs to eliminate priorities, actions, information, data, and funding related to concepts of diversity or disparities among federal agencies as well as federal contractors and grantees.The Office of Personnel Management directed agencies and departments to take down all outward facing media that “inculcate or promote” “gender ideology,” as well as to remove all public facing DEI related websites and content. This resulted in the temporary shutdown of websites and removal of key health datasets. While some web pages and datasets began returning in several days, they included a warning message that they were being modified to comply with President Trump’s executive orders and some materials, such as codebooks and questionnaires, did not immediately return. The administration also directed departments and agencies to pause grants provided to federal contractors to identify and review programs and activities for consistency with the President’s policies. Reports indicate that the administration flagged over 100 words that federal agencies should limit or avoid to comply with the President’s policies, including disparities, diversity, equity, and race; that the CDC ordered the withdrawal of papers pending publication to ensure language compliance; and that research grants were terminated to comply with new restrictions. As part of efforts to eliminate diversity and disparities related initiatives the administration also eliminated environmental justice actions and programs

The administration also eliminated about 10,000 employees from HHS, including many of those focused on addressing disparities as part of a restructuring effort. The HHS Office of Minority Health, CDC’s Office of Health Equity, the Office of Women’s Health, and the Office for Civil Rights are among the offices facing partial or complete cuts. The impact of these cuts is compounded by the loss of population-specific initiatives and offices. The administration’s proposed budget cuts to the Indian Health Services (IHS) and HHS include $900 million in cuts to the IHS budget and eliminating advanced appropriations.  In addition to eliminating staff directly working on disparities, other cuts were made that will have important implications for disparities. The restructuring cut jobs from the CDC’s National Center for Chronic Disease Prevention and Health Promotion, which has resulted in the termination of programs focused on diabetes, obesity, dementia, and kidney disease, which disproportionately affect people of color. The HHS restructuring has also impacted federal maternal and infant health programs, including layoffs of most staff at the CDC’s Division of Reproductive Health, which serves to provide data, research, and assistance to states “on issues related to reproductive health, maternal health, and infant health.” These staff cuts are accompanied by the suspension of the Pregnancy Risk Assessment Monitoring System, which has documented disparities in maternal mortality and morbidity for 38 years.

The actions to eliminate diversity and disparities related initiatives will likely lead to widening disparities, reversing recent efforts to advance health equity. Elimination of focused efforts to address health disparities will potentially further exacerbate disparities, contributing to worsening overall health and unnecessary health care costs. Focused plans and initiatives to mitigate health disparities seek to address the underlying inequities that drive disparities and meet the needs and preferences of diverse populations. In the absence of focused efforts, disparities will likely widen because the underlying inequities that contribute to them persist. Additionally, the elimination of information, data, and research will inhibit the ability to identify disparities and understand the factors driving them. Data are essential for identifying where disparities exist, directing efforts and resources to address disparities as they are identified, measuring progress toward achieving greater equity, and establishing accountability for achieving progress. Without adequate data and research, disparities may remain unseen and unaddressed.

The Trump administration has also made immigration policy changes focused on restricting entry at the border and increasing interior enforcement efforts to support mass deportation, which may contribute to widening disparities among immigrant families. Research suggests that these policies negatively affect the health and well-being of immigrant families, including citizen children living in these families. KFF survey data from 2025 show that immigrants’ worries about detention or deportation have risen sharply since 2023, even among lawfully present immigrants and naturalized citizens, and many say these worries are affecting their health. Moreover, accompanying KFF focus groups  found that immigration policies and actions undertaken by the Trump administration have led to increased fears, uncertainty, and financial hardships among immigrant families across immigration statuses that have had negative effects on their daily lives, health, and well-being, including negative mental health impacts on them and their children. Efforts to restrict immigration not only impact the health and well-being of immigrant families, but can also negatively impact the U.S. economy and workforce, given the role immigrants play, particularly in certain industries such as health care, construction, and agriculture.

Under the recently passed budget reconciliation law there are large cuts to federal spending for Medicaid and the ACA, which will likely lead to widening racial and ethnic disparities in health coverage and, in turn, exacerbate disparities in access to care. Medicaid is a major source of coverage for people of color, helping to fill gaps in employer sponsored coverage, particularly for children (Figure 7). The ACA’s coverage expansions through Medicaid and the Marketplaces contributed to large gains in health coverage across racial and ethnic groups and reduced racial disparities in coverage. The law includes substantial cuts to federal Medicaid spending and changes to the ACA, which the Congressional Budget Office projects will increase the number of uninsured by about 10 million by 2034. The law includes provisions that eliminate eligibility for Medicaid, subsidized ACA Marketplace, and Medicare coverage for many lawfully present immigrants. In addition to reductions in the legislation, the scheduled expiration of tax credits for Marketplace coverage in 2025 and recent Trump administration regulatory changes that make it harder to sign up for ACA coverage are expected to further increase the growth in the uninsured by millions.  Coverage losses, particularly in Medicaid, would widen racial and ethnic disparities in coverage given that larger shares of people of color are covered by the program. In turn, widening disparities in coverage would likely contribute to gaps in access to care and ultimately health outcomes.

Interactive Datawrapper Embed

Future Outlook

Copy link to Future Outlook

Looking to the future, racial and ethnic disparities in health and health care remain a persistent problem, particularly as longstanding efforts to recognize and address them are being dismantled. These disparities are rooted in the ongoing impacts of racism and discrimination, which contribute to structural inequities in access to resources, opportunities, and health care as well as bias within health systems and daily life. As efforts to advance health equity face increasing challenges some key issues include:

How to mitigate bias and disparate treatment in the medical system, amid the growing use of AI and data-driven tools in health care and perpetuation of disproven beliefs about biologic differences by race.

How rollbacks to federal disparities initiatives and DEI programs will impact long term efforts to address disparities in health.

How to close racial and ethnic gaps and prevent further widening of disparities in health coverage and access to care amid efforts to cut Medicaid and other public programs.

What data and research will remain available to identify and understand disparities and develop interventions to address them.

How uneven impacts of climate change and climate-related health risks may impact disparities amid the rollbacks of federal environmental justice efforts.

Resources

Copy link to Resources

Citation

Copy link to Citation

Ndugga, N., Pillai, D., Hill, L., & Artiga, S., Race, Inequality, and Health. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-race-inequality-and-health/ (date accessed).

The Role of Public Opinion Polls in Health Policy

Table of Contents

Introduction

Copy link to Introduction

Polls and surveys are useful tools for understanding health policy issues. However, it takes time and training to understand how to interpret survey results and to decide which polls are useful and which might be misleading. The aim of this chapter is to help you learn how to be a good consumer of polls so they can be a valuable part of your toolkit for understanding the health policy environment. It begins by discussing why polls are an important tool in policy analysis and the caveats to keep in mind when interpreting them. It then discusses polling methodology and the questions you should ask to assess the quality and usefulness of a poll. The chapter ends with some real-world examples in which polling helped inform policy debates.

People sometimes ask if there is a difference between a “poll” and a “survey.” The quick answer is that every poll is a survey, but not every survey is a poll (for example, large federal surveys like the Census or surveys of hospitals or other institutions would not be called polls). For purposes of this chapter, we use the terms interchangeably.

Why Should You Pay Attention to Polls at all?

Copy link to Why Should You Pay Attention to Polls at all?

Polls have gotten a bad rap over the past few years, particularly around election times when they don’t do a perfect job predicting who the winner of a given election will be. Given this, you may wonder why you should pay attention to polls when trying to understand health policy. There are six basic reasons why it’s important for health policy scholars to understand public opinion:

1. People vote, and elections can have important consequences for health policy at the local, state, and national levels. While polls may not always be perfect predictors of election outcomes, they are one of the best ways to understand the dynamics of how voters are thinking and feeling when weighing their vote choices, not only for high-profile offices like President and Congress, but for state and local races and ballot initiatives as well.

2. Public opinion can influence policy choices, particularly for highly salient issues, like health care, that touch pretty much everyone’s lives in some way. While the average member of the public may not be equipped to understand the details of most health policy legislation, their preferences and views can put constraints on lawmakers by identifying actions that would be deemed unacceptable by large majorities of the public or their constituents.

3. Polls can also provide information about the broader environment in which health policy issues or changes are being debated. They can help you understand the salience of a given issue (i.e., how much do people care about prescription drug prices and how closely are they paying attention to debates over how to lower them?) and identify other factors that might affect the likely success of a given policy (i.e., if the country’s attention is focused on a foreign policy crisis, how will that affect the public’s reaction to a major new proposal to overhaul Medicaid?).

4. Beyond measuring opinion, surveys can also be useful for understanding how health policy is affecting people. Survey questions about people’s experiences can offer context by providing information like the share of people who are struggling to afford their health insurance. Looking at questions like these at multiple points in time can also help you understand how experiences change in the months and years following enactment of major health legislation.

5. Surveys can help amplify the voices of real people in policy debates, particularly those that are often ignored or drowned out by special interests. Polling that includes adequate sample sizes to represent the voices of marginalized and underrepresented populations, such as members of racial and ethnic minority groups, immigrants, LGBTQ individuals, people living in rural areas, and those with lower incomes, may be especially useful for understanding the impact of health policy on people.

6. In this way, methodologically sound, non-partisan, transparent surveys can serve as a counterweight to polls sponsored by special interests that are conducted in private and used to craft public messages, design campaigns, or sell products.

Caveats to Polling

Copy link to Caveats to Polling

Polls do not tell the whole story. Public opinion is just one part of the political and policymaking process. Public support for a given policy may seem clear based on a single survey question, but it can be quite malleable in the course of a public debate, and not all surveys measure this malleability. Small changes in survey question wording can sometimes lead to big changes in public support, so it’s important never to rely on a single question from a single poll to make a conclusion about what the public thinks or knows. When possible, look for multiple questions on the same topics from multiple polls conducted at various times. If the answers are consistent, you can be more confident that the conclusion is correct. Sometimes a poll finding conflicts with your best sense of political reality when all available information is considered. In those instances, there’s a good chance your “gut” is a better guide than what a given poll tells you.

There are limits to polling on complex topics like health care. When the public says they support a specific proposal for lowering health care costs, it doesn’t mean they have fully thought through the details of that proposal and its implications. Rather, it may signal how important they think it is for policymakers to address the high cost of health care. And while some polls test this by asking follow-up questions that probe the public about trade-offs to any given policy approach, some health policy topics are just too complicated to reasonably ask the average American to weigh in on in a short survey.

Public opinion can’t give you the “right” answer. While public opinion can tell you where the public stands on an issue, it cannot tell you what the right policy solution is in any given situation. For example, pollsters often ask people to rank the priority they give to different health issues before Congress. They may ask the public to rank the issues of prescription drug costs, the future of the Affordable Care Act, Medicaid expansion, the financial sustainability of Medicare, and so forth. But it turns out that real people aren’t organized like congressional committees and don’t put the issues neatly into policy buckets like pollsters do. What they are concerned about is the cost and affordability of health care, a concern that cuts across these issues. These ranking questions provide some information about what resonates most with the public, but that doesn’t mean they should be treated as a rank-ordered list for policymakers to address starting from the top down. In addition, beyond telling you what the public thinks, polls can be just as useful for pointing out what the public doesn’t understand about a given policy issue, allowing you to direct outreach and education efforts or figure out messaging that will resonate with the public if you are advocating for a policy change.

Understanding the Methods: Questions to Ask about Polls

Copy link to Understanding the Methods: Questions to Ask about Polls

The science of survey research is complicated, but there are a few simple terms you can learn and questions you can ask when you encounter polls in your schooling and daily life. These include:

Population. Who is the population that the survey is claiming to represent? Polls can be conducted with many different populations, so it is important to know how researchers define the population under study. For example, a survey of voters may be useful for your understanding of a particular health care issue’s importance in the election, but it might not be as useful for estimating how many people have had problems paying medical bills, since lower-income people (who may be the most likely to experience bill problems) are less likely to be voters and may be left out of the study entirely.

Sampling. How did researchers reach the participants for their poll, and was it a probability or non-probability sample? In a probability-based sample, all individuals in the population under study have a known chance of being included in the survey. Such samples allow researchers to provide population estimates (within a margin of sampling error) based on a small sample of responses from that population. Examples of probability-based sampling techniques include random digit dialing (RDD), address-based sampling (ABS), registration-based sampling (RBS), and probability-based online panels. Non-probability sampling, sometimes called convenience or opt-in sampling, has become increasingly common in recent years. While non-probability surveys have some advantages for some types of studies (particularly their much lower cost), research has shown that results obtained from non-probability samples generally have greater error than those obtained from probability-based methods, particularly for certain populations.

Data collection (survey mode). While there are many ways to design a survey sample, there are also many ways to collect the data, known as the survey mode. For many years, telephone surveys were considered the gold standard because they combined a probability-based sampling design with a live interviewer. Survey methodology is more complicated now, but it is still important to know whether the data was collected via telephone, online, on paper, or some other way. If phones were used, were responses collected by human interviewers or by an automatic system, sometimes known as interactive voice response (IVR) or a “robocall”? Or were responses collected via text message? Depending on the population represented, different approaches might make the most sense. For example, about 5% of adults in the U.S. are not online, and many others are less comfortable responding to survey questions on a computer or internet-connected device. While young adults may be comfortable responding to a survey via text message, many older adults still prefer to take surveys over the phone with a live interviewer. Some populations feel a greater sense of privacy when taking surveys on paper, while literacy challenges may make a phone survey more appropriate for other populations. Many researchers now combine multiple data collection modes in a single survey to make sure these different segments of the population can be represented.

Language. Was the survey conducted only in English, or were other languages offered? If the survey is attempting to represent a population with lower levels of English language proficiency, this may affect your confidence in the results.

Survey sponsor. Who conducted the survey and who paid for it? Understanding whether there is a political agenda, special interest, or business behind the poll could help you better determine the poll’s purpose as well as its credibility.

Timing. When was the survey conducted? If key events related to the survey topic occurred while the survey was in the field (e.g., an election or a major Supreme Court decision), that might have implications for your interpretation of the results.

Data quality checks. During and after data collection, what data quality checks were implemented to ensure the quality of the results? Most online surveys include special “attention check” questions designed to identify respondents who may have fabricated responses or rushed through the survey without paying attention to the questions being asked. Inclusion of these questions is a good sign that the researchers were following best practices for data collection.

Weighting. Were the results weighted to known population parameters such as age, race and ethnicity, education, and gender? Despite best efforts to draw a representative sample, all surveys are subject to what is known as “non-response bias” which results from the fact that some types of people are more likely to respond to surveys than others. Even the best sampling approaches usually fall short of reaching a representative sample, so researchers apply weighting adjustments to correct for these types of biases in the sample. When reading a survey methodology statement, it should be clear whether the data was weighted, and what source was used for the weighting targets (usually a survey from the Census or another high-quality, representative survey).

Sample size and margin of sampling error. The sample size of a survey (sometimes referred to as the N) is the number of respondents who were interviewed, and the margin of sampling error (MOSE) is a measure of uncertainty around the survey’s results, usually expressed in terms of percentage points. For example, if the survey finds 25% of respondents give a certain answer and the MOSE is plus or minus 3 percentage points, this means that if the survey was repeated 100 times with different samples, the result could be expected to be between 22%-28% in 95 of those samples. In general, a sample size of 1,000 respondents yields a MOSE of about 3 percentage points, while smaller sample sizes result in larger MOSEs and vice versa. Weighting can also affect the MOSE. When reading poll results, it is helpful to look at the N and MOSE not only for the total population surveyed, but for any key subgroups reported. This can help you better understand the level of uncertainty around a given survey estimate. The non-random nature of non-probability surveys makes it inappropriate to calculate a MOSE for these types of polls. Some researchers publish confidence estimates, sometimes called “credibility intervals,” to mimic MOSE as a measure of uncertainty, but they are not the same as a margin of sampling error. It’s also important to note that sampling error is only one source of error in any poll.

Questionnaire. Responses to survey questions can differ greatly based on how the question was phrased and what answer choices were offered, so paying attention to these details is important when evaluating a survey result. Read the question wording and ask yourself – do the answer options seem balanced? Does the question seem to be leading respondents toward a particular answer choice? If the question is on a topic that is less familiar to people, did the question explicitly offer respondents the chance to say they don’t know or are unsure how to answer? If the full questionnaire is available, it can be helpful to look at the questions that came before the question of interest, as information provided in these questions might “prime” respondents to answer in a certain way.

Transparency. There is no “gold seal” of approval for high-quality survey methods. However, in recent years, there has been an increasing focus on how transparent survey organizations are about their methods. The most transparent researchers will release a detailed methodology statement with each poll that answers the questions above, as well as the full questionnaire showing each question in the survey in the order they were asked. If you see a poll released with a one or two-sentence methodology statement and can’t find any additional information, that may indicate that the survey organization is not being transparent with its methods. The American Association for Public Opinion Research has a Transparency Initiative whose members agree to release a standard set of information about all of their surveys. Some news organizations also “vet” polls for transparency before reporting results, but many do not. This means that just because a poll or survey is reported in the news doesn’t necessarily mean it’s reliable. It’s always a good idea to hunt down the original survey report and see if you can find answers to at least some of the questions above before making judgments about the credibility of a poll.

Election polling vs. issue polling. Election polls – those designed at least in part to help predict the outcome of an election – are covered frequently in the media, and election outcomes are often used by journalists and pundits to comment on the accuracy of polling. Issue polls – those designed to understand the public’s views, experiences, and knowledge on different issues – differ from election polls in several important ways. Perhaps the most important difference is that, in addition to the methodological challenges noted above, election polls face the added challenge of predicting who will turn out to vote on election day. Most election polls include questions designed to help with this prediction, and several questions may be combined to create a “likely voter” model, but events or other factors may affect individual voter turnout in ways pollsters can’t anticipate. Election polls conducted months, weeks, or even days before the election also face the risk that voters will change their mind about how to vote between the time they answer the survey and when they fill out their actual ballot. Issue polls do not generally face these challenges, so it’s important to keep in mind that criticisms about the accuracy of election polls may not always apply to other types of polls.

Examples of the Usefulness of Polls in Understanding Health Policy

Copy link to Examples of the Usefulness of Polls in Understanding Health Policy

Example #1: Tracking the evolution of public opinion and experience through debate, passage, and implementation of the Affordable Care Act

The Affordable Care Act (ACA) is the largest health legislation enacted in the 21st century. From the time the legislation was being debated in Congress through its passage, implementation, and efforts to repeal it, the ACA has been the subject of media coverage, political debate, campaign rhetoric, and advertising. In each of those stages, polls and surveys have provided important information for understanding what was happening with the law.

Prior to passage, polls showed the public’s desire for change in health care, particularly when it came to decreasing the uninsured rate and making health care and insurance more affordable. Despite this apparent consensus on the need for change, polls also helped shed light on some of the barriers to passing legislation. For example, survey trends demonstrated how the share of the public who expected health reform legislation to leave their families worse off increased over the course of an increasingly public debate in which opponents tapped into fears about how the proposed law might change the status quo.

After the law was passed, public opinion on the ACA was sharply divided along partisan lines, with majorities of Democrats viewing the law favorably and majorities of Republicans having an unfavorable view. However, surveys also painted a more nuanced picture beyond the overall partisanship, showing that majorities of U.S. adults across partisan lines favored many of the things the ACA did, including allowing young adults to stay on their parents’ insurance until age 26, preventing health plans from charging sick people more than healthy people, and providing financial subsidies to help lower- and moderate-income adults purchase coverage. At the same time, polls showed that many adults were not aware that these provisions were part of the ACA, and that many others incorrectly believed the law did things it did not, such as creating a government-run insurance plan and allowing undocumented immigrants to receive government financial help to purchase coverage.

This combination of “the parts more popular than the whole” and incomplete public knowledge of the law provided some insight into why efforts to repeal the law were ultimately unsuccessful despite the relative unpopularity and deep partisan divisions on the law overall. When faced with the very real prospect of the popular parts of the law going away – particularly the protections for people with pre-existing health conditions – the public (and particularly Democrats and independents who had previously expressed lukewarm support) rallied to protect it. In fact, following concerted Republican efforts to repeal the law in 2017, the ACA has remained more popular than ever, with more adults expressing a favorable than an unfavorable opinion.

In addition to providing information about the public’s evolving opinion and awareness of the law, surveys also helped provide information about people’s experiences under the law. For example, a 2014 survey of people who purchase their own insurance found that 6 in 10 people enrolled in insurance through the new marketplaces were previously uninsured, and that most of this group said they decided to purchase insurance because of the ACA. Subsequent surveys showed that most marketplace enrollees were satisfied with their plans, but many reported challenges related to the affordability of coverage and care.

These are just a few examples of the ways surveys helped provide insights into the dynamics of a complex health policy at different points in time.

Example #2: Understand the limits of public support of Medicare-for-All proposals

Another health policy issue where polls have provided useful information is the debate over a national, single-payer health plan. While the idea has been discussed for decades, public discussion was prominent most recently during the 2016 and 2020 Democratic presidential primaries, when Senator Bernie Sanders made “Medicare-for-all” a centerpiece of his campaign. Since 2017, a majority of U.S. adults have supported the idea of a national Medicare-for-all plan, but once again, polls also indicated why such a proposal had never become a political reality. For example, the public’s reaction to the idea varies considerably based on the language used to describe it; while majorities view the terms “universal coverage” and “Medicare-for-all” positively, most have a negative reaction to “socialized medicine,” and many are unsure how they feel about the term “single-payer health insurance.” Surveys also demonstrate that while support starts out high, many people say they would oppose a Medicare-for-all plan if they heard common arguments made by opponents, such as that it would lead to delays in treatments, threaten the current Medicare program, or increase taxes. Polls like these and others that test different messages can help shed light on the public’s likely reaction to real-world debates over policies, helping us understand some of the reasons why certain policies that seem to attract majority support in the abstract face an uphill battle once public debate and discussion about them begin.

Example #3: Understanding the impact of the Supreme Court’s overturning of Roe v. Wade

Polls can also help shed light when sudden events create policy changes that immediately affect individuals’ access to health care in different scenarios. A recent example is the Supreme Court 2022 decision in Dobbs v. Jackson that overturned Roe v. Wade and eliminated the nationwide right to abortion that had been in place since 1973. The Dobbs decision opened the door for states to pass their own abortion regulations, and many states had previously established “trigger laws” that made abortion illegal as soon as Roe was overturned.

Polls before and after the 2022 midterm election indicated how the overturn of Roe affected voter motivation, turnout, and vote choice. For example, polling in October 2022 showed abortion increasing as a motivating issue for voters, particularly among Democrats and those living in states where abortion was newly illegal. And election polling of voters showed how the Supreme Court decision played a key role in motivating turnout among key voting blocs that likely contributed to the Democratic party’s stronger-than-expected performance in the midterms. Two years later, amid growing economic concerns, polls leading up to the 2024 election showed that while the economy and inflation were far and away the top issues for voters, some key groups of women voters as well as voters in states with abortion-related ballot initiatives continued to be motivated by the issue of abortion more than two years after the Dobbs decision.

Understanding the impact of Dobbs is an area where polling of specific populations (including grouping individuals by the abortion laws in their state) is more useful than looking at the U.S. population as a whole. For example, in addition to shedding light on the dynamics of abortion as an election issue, polling in 2023 indicated widespread confusion about the legality of medication abortion, particularly among people living in states that had banned or severely limited the procedure. Surveys also shed light on the experiences of people living in different states; for example, a 2024 survey found that 1 in 5 women of reproductive age (18-49) living in states with abortion bans said either they or someone they know had difficulty accessing an abortion since the Supreme Court overturned Roe v. Wade due to restrictions in their state.

Example #4: Amplifying the voices and experiences of marginalized populations

Well-designed surveys of under-represented groups can provide important information about health policy by amplifying the opinions and experiences of those whose voices are often left out of policy debates. Examples include:

  • A survey of 2023 Medicaid enrollees documented the coverage status of people who were disenrolled during the Medicaid “unwinding” process. Beginning in March 2020, states kept people enrolled in Medicaid without the need to renew or re-determine eligibility under a law passed in response to the COVID-19 pandemic. When the law expired in March 2023, it was uncertain how individuals and families would be affected. Surveys like this helped document the impact of the policy change on people’s coverage status and access to care.
  • A survey of U.S. immigrants shed light on the health and health care experiences of a group that makes up one-sixth of the adult population. Among other findings, this survey showed that half of all likely undocumented immigrants in the U.S. lacked health insurance coverage, information not previously available from other data sources. It also illustrated the importance of state policies in determining coverage rates for immigrant adults, documenting the much higher uninsured rate among immigrants living in states with less expansive coverage policies (like Texas) compared to those in states with more expansive policies (like California).
  • A survey of trans adults documented this population’s struggles accessing appropriate health care. Among other findings, this survey found that almost 4 in 10 trans adults said it was difficult to find a health care provider who treats them with dignity and respect, 3 in 10 said they had to teach a provider about trans people in order to get appropriate care, and 1 in 5 had health insurance that would not cover gender-affirming treatment. Importantly, these survey findings help increase understanding of the health care experiences of a group that is often marginalized in U.S. society, and one that also faces other barriers, including economic challenges, higher rates of mental health challenges and unmet needs for mental health care.
  • A survey focused on racism, discrimination, and health showed the extent of discrimination and unfair treatment in health care settings. This survey found that large shares of Black, Hispanic, Asian, and American Indian and Alaska Native adults reported preparing for possible insults or being very careful about their appearance in order to be treated fairly during health care encounters. It also showed how individuals who have more visits with providers who share their racial and ethnic background report more positive health care experiences. These findings provide insights into possible policy solutions to improve care, highlighting the importance of a diverse health care workforce that is trained in culturally appropriate care.
  • Surveys of areas impacted by natural disasters also help provide information to guide recovery efforts in these areas. For example, a survey of Hurricane Katrina evacuees living in Houston-area shelters documented the physical and emotional toll of the storm and the disproportionate impact on lower-income, African American, and uninsured residents. A series of surveys of New Orleans residents in the years following Katrina showed steady progress in many areas of recovery, but highlighted how the gap between the experiences of the city’s Black and White residents grew over time in many ways. Surveys of Puerto Rico residents following Hurricane Maria and Texas Gulf Coast residents following Hurricane Harvey provided similar insights to shine a lens on disparities and highlight the needs of the local populations in those areas.

Resources

Copy link to Resources

Citation

Copy link to Citation

Brodie, M., Hamel, L., & Kirzinger, A., The Role of Public Opinion Polls in Health Policy. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-the-role-of-public-opinion-polls-in-health-policy (date accessed).

The Regulation of Private Health Insurance

Table of Contents

Introduction

Copy link to Introduction

Private health coverage is subject to significant requirements at the state and federal levels. While the Affordable Care Act (ACA) of 2010 ushered in many new requirements for the federal regulation of private health coverage, another federal law, the Employee Retirement Income Security Act (ERISA), has for over 50 years regulated the most predominant form of health coverage for people under age 65, employer-sponsored coverage.

States have traditionally been the primary regulators of health insurance, and state health insurance protections continue to play a major role alongside a growing list of federal protections aimed at addressing a variety of consumer concerns, including access to coverage, affordability, and adequacy. This chapter describes the landscape of laws and regulations that address health care coverage and the complicated interactions between state and federal requirements that can make these protections challenging for consumers to navigate. In this chapter, it is not possible to cover every single state and federal requirement for private plans, so the focus is on the primary laws and regulations that apply to private insurance coverage.

Timeline of Major Federal Laws for Private Health Insurance (Scatter Plot)

What Is Private Health Insurance?

Copy link to What Is Private Health Insurance?

Private health coverage is a mechanism for people to finance the health care services and medications they need, protecting them from the potentially extreme financial costs of this care.

At its core, health coverage is a financial contract between a private organization insuring the risk of loss and a policyholder. Where those insuring the risk or paying health claims are private entities such as insurance companies or private employers, this coverage is considered “private.” Coverage available in Health Insurance Marketplaces created by the ACA is considered private coverage, even though the Marketplaces are administered by state or federal government agencies. Public coverage, by contrast, involves financing arrangements for programs such as Medicare and Medicaid, which are paid primarily from public sources. This includes private plans participating in Medicare Advantage and Medicaid managed care arrangements. (See the chapters on Medicare and Medicaid for more information.)

A fundamental concept for the private provision of health coverage is pooling the health care “risk” of a group of people to make the costs of coverage more predictable and manageable. The goal typically is to maintain a risk pool of people whose health, on average, is the same as that of the general population. Private health coverage regulation has historically included steps to prevent insurers and plan sponsors from avoiding people in poor health, while also ensuring that risk pools include people in good health to guard against “adverse selection.”

A risk pool with adverse selection that attracts a disproportionate share of people in poor health, who are more likely to seek health coverage than people who are healthy, will result in increased costs to cover those in the pool, leaving those in better health to seek out a pool with lower costs.

Sources of private coverage. An individual with private coverage generally obtains it through one of two sources, either through their employer (“group” coverage) or by directly purchasing it from an insurer (“nongroup” coverage). Other related sources of coverage don’t exactly fit into one of these two categories, such as coverage provided by professional associations.

1. Employer coverage: In 2023, about 165 million people under age 65 had coverage through an employer. Employer-sponsored coverage is offered to eligible employees and usually to employees’ dependents, such as spouses and children. This coverage is referred to as “group” coverage, which is further broken down into small-group or large-group depending on the number of employees (Figure 1).

Private employers who “sponsor” group health plan coverage could include a range of entities, from a single nationwide retail employer with thousands of employees in many states to a small “mom and pop” operation with a handful of employees in one location. A single union can also be a group health plan sponsor of private coverage as an “employee organization,” as well as entities called “multiemployer” plans that are collectively bargained entities run by a joint board of trustees from labor and management that oversee collectively bargained benefits provided to employees of more than one employer, often in the same industry (for example, hotel workers or skilled workers in the building trades).

Public employers—federal, state, or local government—also sponsor group health coverage. The Federal Employee Health Benefit (FEHB) Program is the largest employer-sponsored health plan in the US. State and local government health plans are often referred to as non-federal governmental plans.

Employers, private and public, have at least two approaches to make coverage available to employees:

  • Fully-insured. An employer can purchase coverage from an insurer to cover their employees for a set premium. In this “fully-insured” arrangement, the insurer bears the financial risk if that group of employees ends up costing more than expected; these plans are regulated by the state in which they are sold. Each state has a group market for the sale of health insurance that is divided by size of the group for oversight and regulation: large group and small group.
    • Large Group Insurance Market typically involves insurance products sold to employers with 51 or more individuals (employees).
    • Small Group Insurance Market is generally an employer group of 50 or fewer individual employees. Small employers can purchase small group coverage from an insurer or through the state’s health insurance exchange or Small Business Health Options Program (SHOP). In a handful of states, the SHOP is the only place where a small employer can purchase state-regulated small group insurance coverage.
  • Self-insured. Employers can also use a “self-insured” (also often referred to as “self-funded”) arrangement where the employer assumes the financial risk by directly paying all covered claims. The employer typically contracts with a third-party administrator (TPA) to administer benefits by paying claims, designing benefits, establishing provider networks, and coordinating other aspects of coverage. TPAs are some of the same private organizations that provide health insurance as another line of business, as well as organizations called Pharmacy Benefit Managers (PBMs) that administer prescription drug benefits. As a result, coverage may not appear different to the covered worker than if they had fully-insured coverage. As explained in an upcoming section, unlike fully insured health coverage, self-insured coverage provided by private employers is largely not subject to state law but is governed primarily by federal law---mainly ERISA. Self-insuring health benefits are more common among larger employers because they can spread risk over a larger number of enrollees.

2. Individually-purchased insurance coverage: An individual can purchase private health coverage for themselves and their family without the involvement of their employer, referred to as “nongroup” coverage. Every state has an “individual insurance market” that consists of the following:

  • Marketplace. The ACA required the creation of health insurance Marketplaces in each state, where individuals can purchase insurance, with federal financial assistance for premiums and cost sharing if eligible. The coverage purchased from a Marketplace must meet certain minimum standards, including coverage of essential health benefits, no preexisting condition exclusions, and limits on varying premiums based on health status (“ACA-compliant” insurance). (See the ACA chapter for more information.)
  • Off Marketplace. People can also purchase individual insurance outside the Marketplace where federal financial assistance is unavailable. This could include ACA-compliant plans similar to those offered on the health insurance Marketplaces, and other types of coverage or financial products with lower premiums, but less comprehensive coverage than ACA-compliant plans, such as short-term limited duration coverage, fixed and hospital indemnity arrangements, health care sharing ministries, and others.

3. Other Sources of Private Health Coverage: Other sources of health coverage subject to unique regulatory standards include health coverage provided through entities called “multiple employer welfare arrangements” (MEWAs), “church plans,” and coverage provided by colleges and universities for their students.

  • A MEWA is generally any arrangement that provides benefits – in this case, health benefits – to employees of more than one unrelated employer. Historically, MEWAs have been vehicles for organizations to market less expensive health benefits to groups of employers, especially small employers. To address a history of MEWA insolvencies attributed to a lack of proper government oversight, changes to ERISA in 1983 created a complicated regulatory regime just for MEWAs, subjecting them to a mix of federal and state laws.
  • One type of MEWA, also governed by ERISA, allows groups of more than one employer to sponsor health coverage for their employees, known as an “Association Health Plan.” Traditionally, these types of plans have been available to groups of small employers in a similar industry, such as those who sell real estate or work in a similar profession. In recent years, federal efforts to expand the criteria for what types of employers may form an AHP have been the subject of litigation and regulations.
  • Church plans are offered to employees by a church or association of churches, including entities controlled by or associated with a religion, such as religiously-affiliated hospitals and schools. Unlike other employer-sponsored plans, church plans are exempt from most ERISA requirements and some of the ACA’s health reforms. These regulatory gaps in church plans, including coverage of contraception, have been the subject of numerous legal proceedings.
  • A student health plan is any health coverage sponsored by a college or university for students. While it is not group coverage, it can be sponsored by a university in the same way employers sponsor health coverage. The ACA has special rules for this coverage. While an insured arrangement is considered individual market coverage, exceptions allow it to be provided without the insurer having to meet certain ACA market rules. A university can also sponsor a self-insured health plan for students. These arrangements do not have to meet the ACA’s market rules, although states may regulate them.

What Are the Different Types of Private Health Plans?

Copy link to What Are the Different Types of Private Health Plans?

Most private plans utilize a “network” of health care providers and hospitals, with some plans requiring a referral from a primary care provider (PCP) for enrollees to see a specialist. These types of arrangements, referred to as “managed care plans,” attempt to control costs and utilization through financial incentives, development of treatment protocols, prior authorization rules, and (in limited circumstances) dissemination of information on the quality of provider practices. Most private health coverage, whether employer-sponsored or individually purchased, falls into one of the following types:

Types of Private Insurance Plans (Table)

All of these plan types are available in the individual market, both on and off the Marketplace. Most employers that offer health benefits offer just one type of health plan, though larger firms may offer more. PPOs are the most common type of health plan offered by employers.

Other employer-sponsored health coverage arrangements: Employers also can offer a Health Reimbursement Arrangement (HRA), which is an employer-funded group health plan, sometimes paired with a high-deductible health plan (HDHP), that reimburses an employee up to a certain amount for qualified medical expenses and, in some instances, health insurance premiums. Reimbursements are tax-free to the employee, and amounts in the account can carry over to the following year, but employees lose any amounts when they leave the employer. Other variations of HRAs include an Individual Coverage HRA (ICHRA), where an employee can use funds in the HRA to purchase individual insurance either on or off the Marketplace. Qualified Small Employer Health Reimbursement Arrangements (QSEHRAs) are HRAs that certain small employers can make available for tax-free reimbursement of certain expenses.

Health Savings Accounts (HSAs): HSAs are tax-advantaged savings accounts that enrollees in certain HDHPs can use to pay for qualified medical expenses. While the HDHP associated with an HSA is usually sponsored by an employer or obtained through a Marketplace plan, the HSA itself is not usually considered employer-sponsored coverage (in contrast to HRAs). HSAs are owned by the individual and are portable, meaning consumers can carry them from job to job and use them after retirement.

Value-Based Arrangements: Some private health plans utilize “value-based” coverage and alternative payment models. These designs, primarily used in federal Medicare and Medicaid demonstration projects, aim to make providers more accountable for patient outcomes through various financial and other incentives. The objective of value-based care design is to shift the fee-for-service reimbursement model of paying for care based on “volume” to a system that pays based on the “value” of a service. Demonstration results to date have not shown major savings, but these designs are still discussed as a potential cost-containment tool for private health coverage. Payers and providers have also looked to value-based payment models to improve health disparities and to provide more patient-centered care.

How Do Federal and State Regulation of Health Insurance Interact?

Copy link to How Do Federal and State Regulation of Health Insurance Interact?

The regulatory framework for private health coverage has evolved into a complicated system of overlapping state and federal standards. This federalism framework creates a sometimes precarious “marriage” between state and federal authority in order to implement health policy goals.

List summarizing five key features of the regulatory framework for private health insurance. States lead insurance regulation, while federal law establishes a minimum level of protections. ERISA limits the application of state law to private employer-sponsored coverage, and federal requirements vary by the market or source of coverage. Certain types of private coverage are exempt from many insurance protections, and tax policy affects the cost of and access to health care and private insurance coverage.
1. States lead on insurance regulation, but with a federal fallback for most protections.

The regulation of insurance has traditionally been a state responsibility. States license entities that offer private health insurance and have a range of insurance standards, including financial requirements unique to state law. However, the federal government has played an increasingly significant regulatory role over the past 50 years.

The federal pension law, ERISA, passed in 1974, applies to insured and self-insured private employer-sponsored health coverage with similar legal and enforcement mechanisms to protect individuals covered by private group health plans as those created for pension plans.

Separately, the federal Health Insurance Portability and Accountability Act of 1996 (HIPAA) created new federal requirements and the basic framework for how state and federal law now interact. Under this “federal fallback” structure, states may require that insurers in the group and individual market (as well as state and local government self-insured plans) implement federal requirements on health coverage. If a state fails to “substantially enforce” the federal requirements, the federal government will enforce those protections. The federal fallback framework was intended to allow states to continue to regulate private coverage while ensuring that all consumers nationwide have a floor of federal protections when a state fails to implement them.

The federal fallback framework does not apply to self-insured employer-sponsored coverage. The U.S. Department of Labor (DOL) almost exclusively regulates private self-insured employer-sponsored plans. The Center for Medicare and Medicaid Services (CMS) directly enforces federal protections against state and local government self-insured employer plans (although states can also do so).

2. ERISA limits the application of state law for those with private employer-sponsored coverage.

ERISA specifically “preempts” or prevents state law from applying to most self-insured group health plans, limiting the scope and application of state protections for many Americans covered by employer-sponsored plans.

Aspects of this preemption have been the topic of almost 50 years of litigation, resulting in three overall conclusions:

  • Most state insurance laws, including state benefit mandates, don’t apply to self-insured ERISA plans, resulting in fewer regulatory requirements on these plans than on fully-insured plans.
  • State insurance laws generally do apply to fully-insured ERISA plans.
  • ERISA provides exclusive, yet limited, civil remedies for enrollees in ERISA plans who are harmed due to a violation of the law.

Today, some argue that ERISA preemption sustains the employer-based health coverage system because meeting an ever-growing list of state laws would be costly for employers, particularly those with employees in multiple states. Having national uniform standards, they argue, provides employers with an incentive to offer coverage. Others argue that preemption handcuffs states’ ability to protect consumers and control health care costs and that it is no longer needed given the ACA’s employer shared responsibility provision for larger employers and the increased regulation that applies a variety of rules to both fully-insured and self-insured plans. Prospects for change are limited, but some have explored the possibility of alternative approaches.

3.  Federal regulation of private health coverage can differ based on the market/source of coverage.

Private health insurance regulations vary based on the insurance market and the source of coverage. This is in part due to ERISA preemption and the ACA, which applies many reforms only to the individual and small-group markets.

Further complicating this are plans that existed before the ACA was passed, called “grandfathered” plans, that do not have to meet many of the ACA standards, so long as no significant changes in cost sharing and benefits are made to the plan.

The ACA did, however, alter federal law to create a large number of consumer protections that apply many of the same regulatory requirements across almost all sources of private health coverage. (See Table 7.)

Finally, some federal standards only apply to employer-sponsored plans (insured and self-insured) that are governed by ERISA, such as the requirement on employers with 20 or more employees to provide temporary continuation of coverage in certain situations, known as COBRA, which also applies to certain state and local government employers. There are also obligations on plan “fiduciaries” that are unique to ERISA plans.

This all means consumers can have different legal protections with their private coverage based on their coverage type and the state where they live.

4. Special exceptions in regulations allow certain types of private coverage to avoid having to meet many insurance protections.

Some private plans are specifically exempt from most federal private health coverage protections, including the ACA. These forms of coverage are often called “non-ACA compliant” coverage. While “non-ACA compliant” does not automatically mean it is illegal or inappropriate, some forms of this coverage have come under increasing scrutiny by federal and state authorities due to their gaps in consumer protections.

These types of coverage fall into these general categories:

  • Coverage that is an “excepted benefit” is specifically carved out of most of the ACA and other federal requirements. Some are considered health coverage under federal law, such as certain dental and vision benefits, and other forms of coverage may not be, such as fixed and hospital indemnity, cancer-only coverage, accidental death and dismemberment, and long-term care coverage. (This Health Affairs article provides a more detailed description of excepted benefits.)
  • Short-term limited-duration coverage and other forms of coverage are not regulated as health insurance under federal rules (as mentioned in the previous section).
  • Employer-sponsored plans with less than two participants who are current employees. This exception was included in the 1996 HIPAA law and has been interpreted as excluding employer-sponsored plans that cover only retirees from many federal insurance requirements.

Some of these forms of coverage are the focus of business promoters looking to market cheaper, largely unregulated forms of coverage. In some instances, this coverage might be promoted by unscrupulous actors who falsely market the coverage as meeting ACA requirements or as providing comprehensive coverage. In other cases, coverage is sold as supplemental “health” coverage along with ACA-compliant health insurance, sometimes with very high deductibles. These exceptions to the ACA’s broad coverage requirements can operate as loopholes in the implementation of consumer health coverage protections and may create ambiguities for consumers as well as employers.

5. Tax regulation matters for cost and access to health care and coverage.

Central to evaluating how private coverage works are the tax subsidies that reduce the cost of coverage and benefits, which can incentivize employers to sponsor and individuals to purchase private health coverage. Tax regulations also interpret what medical expenses (as opposed to general wellness or other non-medical expenses) get a tax preference.

The largest health care tax subsidy is applied to employer-sponsored coverage. Tax-exempt employer contributions for medical insurance premiums and medical care resulted in more than $224 billion in lost revenue for the federal government in 2022. Employer-sponsored health coverage is excluded from federal income tax, as well as federal employment taxes (and equivalent state taxes). The exclusion also applies to amounts reimbursed to employees by an employer under arrangements called “health flexible spending arrangements” (health FSAs), where an employee elects to have amounts withheld from their wages to pay for medical expenses. The exclusion provides considerable tax savings for employers and employees making contributions toward health coverage. The value of this exclusion increases as income increases, making income tax savings greater for higher-income individuals than for lower-income individuals. For various policy reasons, including to rein in health care costs, there have been efforts to change or cap this exclusion over the years, but to date, none have been successful. The most recent, the “Cadillac tax” provision of the ACA, was removed from the law before it was implemented (see the Employer-Sponsored Health Insurance chapter).

Additionally, the ACA created refundable tax credits based on household income to help individuals purchase coverage on a health insurance Marketplace (see the Affordable Care Act chapter). In contrast to the employer exclusion, tax subsidies for Marketplace participants are higher for those with lower incomes. Temporary increases in these credit amounts, passed as part of the American Rescue Plan and the Inflation Reduction Act, have led to record Marketplace enrollment. Unless Congress extends them, the temporary increases expire at the end of 2025. Unlike employer-sponsored insurance, Marketplace enrollees who pay a premium for their individual market insurance coverage generally do so with after-tax dollars (although an employer can sponsor tax-advantaged ICHRAs or QSEHRAs, as described above, to help employees pay for Marketplace and other individual market coverage).

In addition to the tax advantages related to employer-sponsored health coverage and tax subsidies received by lower-income individuals with Marketplace coverage, HSAs bring their own set of tax advantages for those who use funds in the account to pay for cost sharing and for items the IRS includes as qualified medical expenses. In 2025, a federal budget reconciliation law was enacted that may increase the use of HSAs.

What Federal Requirements Apply to Health Insurance?

Copy link to What Federal Requirements Apply to Health Insurance?

The scope and extent of federal regulation affecting private health coverage has vastly increased, especially with the passage of the Affordable Care Act (ACA) in 2010. The ACA largely retained the framework for the regulation of private coverage, adding a long list of new provisions to different regulated pieces of our fragmented health care system. This means specific and overlapping requirements on insurers, employer-sponsored plans, and, more recently, in the No Surprises Act, also on providers.

The ACA also unleashed a firestorm of activity resulting from longstanding political and philosophical differences on the role of federal government regulation of health care. Efforts to repeal and replace the ACA in 2017, several U.S. Supreme Court cases challenging ACA provisions, and hundreds of other cases in the lower courts on the ACA and other federal requirements mean the law in this area has and will continue to be in flux.

Regulatory priorities can and have shifted depending on what party controls the White House and Congress, resulting in ever-changing federal standards. This section reviews the current landscape of federal requirements. A discussion of every single relevant federal regulation is beyond the scope of this chapter, but the major requirements have been divided into six categories:

  • Access to health coverage
  • Affordability of health coverage
  • Benefit design and adequacy
  • Reporting and disclosure of information concerning coverage
  • Review and appeal of health claims
  • Other federal standards
1. Access to coverage

Federal health care reform has prioritized expanding health coverage to those without it for quite some time, especially for those not eligible for a public program such as Medicaid or Medicare, or who do not have coverage through their current employer. Prior to the passage of the Affordable Care Act in 2010, state laws and regulations were designed to address the potential for adverse selection in health insurance by allowing insurers to engage in certain practices such as “underwriting,” which allowed insurers in the individual and group markets to decline to cover or renew coverage due to a person’s health status or a group’s claims history, and helped plans maintain predictable and stable risk pools. Further, an insurer could cover the applicant, but charge a higher premium based on age, health status, gender, occupation, or geographic location. In addition, insurers could exclude benefits for certain health conditions if the person was diagnosed or treated for that condition before becoming insured (a “preexisting condition exclusion”).

States made some reforms, particularly in the small group market, to address these barriers to coverage. Some of these changes became part of the federal Health Insurance Portability and Accountability Act (HIPAA) of 1996. However, it was not until the ACA that the regulation of private insurance, at least for the individual and small group markets, was fundamentally changed.

Core Private Insurance Coverage Protections. The ACA established core market rules designed to expand coverage to most people in the U.S. New ACA legal requirements include:

Table summarizing major consumer protections in private health insurance coverage. The protections include guaranteed issue, which requires plans to accept eligible applicants; guaranteed renewability, which generally requires plans to renew coverage except in limited circumstances such as fraud or nonpayment of premiums; bans on using health status or genetic information to determine eligibility or premiums in the individual and small-group markets; restrictions on premium variation, allowing differences only based on factors such as age, tobacco use, geographic area, and enrollment type; prohibitions on pre-existing condition exclusions; and prohibitions on rescissions, preventing plans from retroactively canceling coverage except in cases of fraud or intentional misrepresentation.

Requirements for premium stabilization and other efforts to protect the risk pool. The ACA’s private insurance market regulations also ushered in concerns that its protections, including guaranteed issue and the elimination of health underwriting for some coverage, would result in adverse selection (discussed in the first section). Regulatory efforts to prevent adverse selection have also focused on certain plans and products that do not have to meet most of the ACA rules, such as short-term limited-duration plans. Non-ACA-compliant coverage may be attractive to consumers looking for lower monthly costs, but these plans can leave consumers underinsured and may compromise the risk pool by drawing out healthier individuals.

Federal guidance and regulation aimed at protecting the risk pool as part of the ACA include:

Table summarizing Affordable Care Act provisions designed to protect and stabilize insurance risk pools. The table highlights three key approaches: the individual mandate, which originally required most U.S. citizens and legal residents to maintain minimum essential coverage and still affects eligibility for certain special enrollment periods; premium stabilization programs, including temporary reinsurance and risk corridors and a permanent risk adjustment program to reduce uncertainty in the individual and small-group markets; and the employer mandate, which requires large employers to offer affordable health coverage meeting minimum value standards or potentially face penalties when employees receive Marketplace premium tax credits.

Standards to prevent coverage gaps. Access to coverage is also enhanced by federal requirements to provide for the continuity of coverage or care to prevent gaps for those who do or could lose coverage, including:

Table outlining key private insurance protections designed to prevent interruptions in health coverage. Protections include dependent coverage for young adults up to age 26, continuation coverage under COBRA for people who lose coverage because of events such as job loss, reduced work hours, or divorce, special enrollment periods that allow individuals to enroll in or change coverage after qualifying life events outside the regular open enrollment period, and continuity-of-care protections that allow some patients to continue receiving care from a provider who leaves their plan’s network. The table emphasizes mechanisms that help individuals maintain or transition health coverage when life circumstances change.
2. Financial Protection and Affordability

High costs, in the form of both premiums and cost sharing, have been a defining feature of employer-sponsored and individually-purchased (for unsubsidized enrollees) health coverage. Federal reforms have sought to address the stability and affordability of health insurance. Key provisions include:

Federal Insurance Financial and Affordability Protections (Table)
3. Benefit Design and Adequacy

Federal requirements also include a list of minimum standards for how a plan is designed or operated in an effort to ensure that enrollees have coverage that is comprehensive enough to cover medically necessary care, with processes that do not unnecessarily limit access to covered benefits. Such requirements include laws that prohibit plans from imposing annual dollar limits on coverage or requiring waiting periods longer than 90 days before employer-sponsored coverage kicks in. States may have additional benefit mandates for state-regulated plans, such as comprehensive coverage requirements for mental health or substance use disorders or fertility services.

Required coverage.

The ACA requires all private, non-grandfathered health plans to cover preventive services with no cost sharing for enrollees. These requirements change over time as preventive service recommendations are updated and new services are added. In general, these include:

Table describing the four categories of ACA preventive service requirements for private health plans: services rated A or B by the U.S. Preventive Services Task Force; immunizations for children, adolescents and adults recommended by the CDC’s Advisory Committee on Immunization Practices; preventive care for children and adolescents supported by the Health Resources and Services Administration; and women’s preventive care and screening services, including contraception, determined by the Women’s Preventive Services Initiative.

The preventive care coverage requirement has been the subject of extensive litigation since the ACA was passed. KFF briefs provide more detail on this litigation and a 2025 U.S. Supreme Court decision involving ACA preventive care standards. The contraceptive coverage requirement has been the topic of two U.S. Supreme Court cases and several regulations, now allowing employers to not cover contraception if they have a religious objection.

Other required design standards across most health plans.

Large group, small group, individual, and self-insured health plans are required to abide by other benefit design standards that aim to contain out-of-pocket costs and improve access to quality care. These design standards include:

Design Standards That Apply to Most Health Plans

Design standards limited to individual and small group plans. Federal requirements on health plan design standards for certain segments of the individual and small-group markets have evolved since the ACA was passed. Plans must meet these rules as part of annual certification requirements for qualified health plans. Examples of these standards include:

Design Standards for Individual and/or Small Group Health Plans (Table)
4. Disclosure, Reporting and Transparency

The 2023 KFF Survey of Consumer Experiences with Health Insurance found that most Marketplace and employer-sponsored insurance (ESI) enrollees reported difficulty understanding some aspect of their health insurance compared to consumers enrolled in Medicaid and Medicare:

Grouped bar chart comparing the share of insured adults who say key aspects of their health insurance are somewhat or very difficult to understand across employer-sponsored insurance (ESI), Marketplace, Medicaid, and Medicare coverage. Marketplace enrollees are most likely to report difficulty understanding what their insurance covers (46%), out-of-pocket costs (41%), and explanations of benefits (38%), followed by ESI enrollees (40%, 34%, and 35%, respectively). Smaller shares of Medicaid and Medicare enrollees report difficulty with these topics. Across all coverage types, understanding what insurance will and will not cover is the aspect most commonly cited as difficult, indicating that many insured adults struggle to understand important features of their health coverage.

Lack of information or understanding about key features of an individual’s health coverage can put patients at financial risk and result in negative health outcomes. Employers and other health purchasers have also struggled to get the information they need to make prudent decisions about cost-effective coverage options and hold their service providers accountable for their plan designs, contracting, and administration activities. Regulations have increased over time to make more information available to enrollees or prospective enrollees, as well as to federal agencies to conduct their oversight responsibilities. What to disclose and how much information is useful is a continuing policy challenge.

Most federal disclosure, reporting, and transparency requirements fall into two categories: Disclosure of information to enrollees and/or the public (Table 9) and reporting to the federal government (Table 10). Note that the requirements provided in these tables are not exhaustive, but include examples of some of the main reporting, disclosure, and transparency requirements that plans, providers, and facilities are subject to.

Disclosure of Information to Enrollees and/or the Public (Table)

Ongoing reporting by private plans to federal agencies is a tool for agency oversight to assess compliance with regulations and evaluate trends. In some instances, agencies are required to use this information to report aggregate information to the public and Congress.

Requirements for Reporting to the Federal Government (Table)
5. Claims and Appeals Processes

Access to a fair system of review for consumer grievances about plan actions and claims denials has been a key element of federal consumer protection.

A 1997 Clinton Administration initiative, the Patient Bill of Rights, resulted in several federal agencies taking regulatory actions to enhance consumer protections for patients and workers. As part of this initiative, the DOL updated claims and appeals rules that applied to private-sector employer plans regulated by ERISA to make the claims review process:

  • Faster (shortened timeframe for plans to make a decision on claims and appeals)
  • Fairer (ensure plan decision makers were free of conflicts of interest)
  • Fuller (more transparent through the disclosure of more information to consumers–including language access standards–about the reason for a claim denial)

The DOL issued regulations in 2000 governing the “internal” claims review process, conducted internally by a plan or plan-sponsor employer. For the first time, these updated rules accounted for managed care features such as prior authorization, where health plans determine medical necessity before the plan covers an item or service, requiring, for example, shorter time frames for claim decisions and appeals for these “pre-service” claims.

Table summarizing timelines for private health plans’ to notify consumers of internal appeals decisions. Enrollees generally have 180 days to file an internal appeal regardless of whether the appeal is urgent, pre-service, or post-service. Plans must make decisions and notify consumers on urgent appeals within 72 hours. For pre-service appeals, plans must issue a decision within 30 days for a single appeal and within 15 days for a second-level appeal. For post-service appeals, plans must issue a decision within 60 days for a single appeal and within 30 days for a second-level appeal. The table highlights the shorter time frame for urgent appeals and pre-service claims (prior authorization decisions) compared to claims for services already provided.

These rules were the basis for reforms applied across all private health coverage in the ACA. These reforms established a federal floor of protections for the internal claims and appeals process and added an option for consumers to appeal denied claims through an “external review” by an entity independent of the plan. Only certain types of claims, such as those that involve clinical judgment, are eligible for external review.

Policymakers have renewed scrutiny of the prior authorization process, as well as claims review and appeals generally. Claims and appeals standards that apply to Medicare Advantage plans, Medicaid, and some Marketplace plans were updated in 2024 to reduce delays in decision-making and to provide more transparency about the outcomes of claims and appeals decisions.

6. Other Federal Standards

Several other federal laws and regulations provide consumer protections in private health insurance, often indirectly, that sometimes have stronger enforcement mechanisms and penalties than federal insurance laws. These include:

Civil Rights Law. The Civil Rights Act of 1964 (and later amendments to it, including the Pregnancy Nondiscrimination Act) and the Americans With Disabilities Act of 1990 created protections against discrimination based on race, color, national origin, sex, age, and disability. At a minimum, these standards apply to employers with 15 or more employees, and, in effect, regulate those employers’ group health plan coverage.

Section 1557 of the ACA is a nondiscrimination provision that potentially applies many existing civil rights laws directly to health care entities, including insurers that receive federal funds. The extent of its reach has been the subject of several sets of regulations, with the iteration issued by the Biden administration addressing Section 1557’s ban on sex discrimination (among other issues) and reinstating protections against discrimination for LGBTQ+ people seeking health care and coverage, including for gender-affirming care. Trump administration actions will likely seek to undo this requirement and place restrictions on gender affirming care that the courts will be tasked with evaluating in the years to come.

Antitrust Laws. Antitrust laws in health care prohibit anticompetitive practices and mergers by health care providers, hospitals, and insurers, which can reduce competition and increase prices. As provider consolidation increases, federal agencies such as the Department of Justice (DOJ) and the Federal Trade Commission (FTC) have engaged in enforcement initiatives in recent years. Health insurers have also faced antitrust scrutiny as the market shares of the largest health insurers continue to dominate in most locations. Oversight of pharmacy benefit managers, now mostly owned by or affiliated with the largest health insurers, is one area of focus where Congress continues to debate whether additional standards are warranted, and state attorneys General are increasingly focusing their attention.

Privacy Laws. As digital health technology has advanced, so have concerns about protecting consumer health information, as the fast development of new technology (e.g., health-related apps, artificial intelligence) has made it difficult for regulation to keep up. The leading federal privacy requirements for health plans’ use of certain patient information, set out in HIPAA regulations, are now almost 25 years old. Efforts to update this regulation have been discussed, but have not yet been finalized. Updates to the HIPAA privacy rules were proposed toward the end of the first Trump administration. Updates to HIPAA’s security standards were proposed at the end of the Biden administration. It is unclear whether renewed proposals in this area are imminent. Regulatory changes to HIPAA in 2023 aimed at clarifying reproductive health care privacy were struck down by a federal court in 2025. The FTC has sought to regulate areas not covered directly by HIPAA, such as software applications increasingly marketed as part of health coverage. Continuing federal efforts to advance electronic information sharing (known as "interoperability") will mean renewed calls for increased federal privacy and security protections.

Special privacy protections for substance use disorder information are regulated under a law known as “Part 2.” This law aims to protect the confidentiality of this information while still allowing providers to share patients’ mental health and substance use disorder information with plans and others to coordinate care and administer benefits.

Gag Clauses. Plans and issuers are prohibited from entering into an agreement with a provider, third-party administrator, or other service provider (including pharmacy benefit managers) that restricts the plan and issuer from accessing claim, cost, or quality information on providers, enrollees, plan sponsors, and other entities, known as a “gag clause.” Plans and issuers must annually submit an attestation of compliance with these requirements to the federal government.

Who Regulates Health Insurance at the Federal Level?

Copy link to Who Regulates Health Insurance at the Federal Level?

Three federal agencies have overlapping jurisdiction for most federal regulation of private health plans: the U.S. Department of Health and Human Services (HHS), the U.S. Department of Labor (DOL), and the U.S. Treasury Department. Through a structure created by HIPAA in 1996, these three agencies jointly issue regulations and other guidance on laws passed by Congress that place the same or similar standards across all private plans.

The same or similar federal requirements for private health plans are typically contained in three separate statutes that each agency oversees:

As an example, if Congress passes a federal law that requires all insurers of individual and group coverage and all employer-sponsored plans to meet a certain standard, any regulations issued to implement that standard are usually issued jointly by HHS, DOL, and Treasury with separate but identical language added to the Public Health Service Act (PHSA), ERISA, and the Internal Revenue Code (IRC). However, each agency has its own requirements for how these laws are enforced. In addition to these overlapping authorities, each of these three agencies has exclusive federal authority over certain aspects of private health insurance regulation (though the federal authority might be shared with states in some instances):

Table summarizing federal agency enforcement responsibilities for private health plan requirements. HHS, through CMS and CCIIO, administers the Public Health Service Act and enforces requirements for insurers as a federal fallback when states do not substantially enforce them, as well as for self-insured, non-federal governmental plans. The Department of Labor, through EBSA, administers ERISA requirements for private employer-sponsored plans, including reporting, disclosure, COBRA, fiduciary and ACA consumer protection requirements. The Treasury Department, through the IRS, administers the Internal Revenue Code and enforces requirements related to ACA premium tax credits, employer shared responsibility, charity care, health savings accounts, COBRA and civil penalties for ACA consumer protections.

Other agencies with important oversight roles of private health coverage include:

  • HHS’s Office of Civil Rights: Implements HIPAA’s administrative simplification standards; ACA section 1557 nondiscrimination rules
  • HHS’s Office of the National Coordinator: Coordinates efforts to implement and use health information technology and health information exchange
  • HHS’s Food and Drug Administration: Regulates clinical investigations and supervises the safety of pharmaceutical drugs, biological products, and medical devices
  • Department of Justice: Antitrust enforcement
  • Federal Trade Commission: Antitrust enforcement
  • Equal Employment Opportunity Commission (EEOC): Nondiscrimination in health coverage and wellness program standards

How Are Federal Health Insurance Requirements Implemented and Enforced?

Copy link to How Are Federal Health Insurance Requirements Implemented and Enforced?

As the executive branch of the U.S. government, the federal government has the authority to execute laws passed by Congress and signed by the President, including issuing regulations to operationalize and implement a statute. In addition, specific agencies have the authority to investigate violations of the law and enforce the law through policy form review, market conduct exams, assessment of penalties, and/or bringing a court action to stop an insurer from violating the law (called an injunction).

Regulations and Other Guidance

Process: The federal regulatory process is governed primarily by the Administrative Procedure Act (APA). This law, along with specific executive orders, governs the process known as “notice and comment rulemaking,” where regulations are proposed (through a notice of proposed rulemaking or “NPRM”) and are subject to public comment for a certain period of time and then finalized. The process is administered by the Office of Management and Budget (OMB), an agency within the Executive Office of the President. The OMB’s Office of Information and Regulatory Affairs (OIRA) coordinates the review and release of regulations from the agencies. Regulations are published in the Federal Register, a daily publication of regulations and notices. Information about regulations under OIRA review is available by agency at Reginfo.gov, and the public can view all regulations and comment letters at Regulations.gov. Twice a year, OMB issues a regulatory agenda of regulations agencies expect to publish in the coming months.

Authority: Once a regulation has gone through the notice and comment process and a final rule is issued, it is generally considered to have the force of law, meaning private actors must comply with it, and individuals can rely on having the protections set out in the law and the regulation. However, regulations are subject to legal challenge under the APA if they are inconsistent with the statute.

Review of regulations by courts: Traditionally, if a regulation interprets a part of a statute that was not clear as drafted by Congress, and a federal court reviews a challenge to the regulation, the court would uphold the interpretation in a regulation unless it is unreasonable or arbitrary. Essentially, courts deferred to the expertise of government regulators and the regulatory review process to uphold a regulatory requirement if they deemed the interpretation reasonable. This practice is called “Chevron deference,” named after a Supreme Court case from 1984, Chevron v. Natural Resources Defense Council, that set out the framework for court review of ambiguous language in a statute. This standard of review can result in agencies having discretion to implement policy changes through the interpretation of regulation. That discretion was challenged in recent years as too broad, giving regulators too much authority, and in June 2024, the U.S. Supreme Court overruled its previous decision, meaning federal courts are no longer required to defer to regulations of administrative agencies in circumstances where they traditionally would have. Eliminating Chevron deference could weaken the impact of regulation on public policy and shift more policy decisions to courts.

Sub-regulatory guidance: Other types of information and guidance commonly issued by a federal agency that do not go through the formal regulatory notice and comment process are referred to as “sub-regulatory.” Information and interpretation in sub-regulatory guidance usually do not have the force of law as regulations do, and typically do not create legally binding obligations on private parties. They are, however, useful in quickly communicating information to regulated entities and the public to signal how and when the agency plans to implement a new law, and the timing of that implementation. However, reliance on these types of guidance by consumers has its limits since regulated entities might still assert that this type of guidance is not binding on them. Examples of sub-regulatory guidance include:

  • Frequently asked questions, manuals, memos, and letters used by CMS, DOL, and the IRS: Certain provisions of the ACA have been the subject of numerous sub-regulatory guidance, including over 60 pieces of guidance in the form of frequently asked questions issued jointly by CMS, DOL, and the IRS. Sub-regulatory guidance also includes implementation manuals, policy letters, and enforcement memos.
  • Advisory opinion or information letters: The DOL and IRS have used advisory or information letters and chief counsel notices to address fact-specific questions at the request of regulated entities. DOL and IRS responses to these inquiries only apply to the specific parties and scenarios addressed, so they can’t be relied on by the public and can create ambiguities about what the law requires, which can remain unresolved for years until formal regulations are finalized. Note that the IRS also has several other types of guidance with varying levels of authority.

Enforcement

Given the federal fallback framework described in previous sections, the enforcement mechanism for most federal requirements on private coverage depends on the type of health plan and the federal agency enforcing the requirement, as summarized in Table 13 below.

Government enforcement. Under the existing federal fallback framework, CMS has developed a process for determining whether a state is substantially enforcing each specific federal insurance protection. This means that whether a state or CMS is responsible for enforcement can differ for each health coverage standard, resulting in a patchwork of federal and state enforcement responsibilities. In addition, both the DOL and the IRS each have their own separate enforcement processes for the federal standards they implement.

Private Right of Action and Remedies. Some laws also allow individual consumers or their representatives to bring a lawsuit independent of the government to address a violation. These laws may detail what types of “remedies” are available if the challenge is successful---for example, an injunction to stop a violation, a civil penalty, or compensatory or punitive damages. Without this “private right of action,” aggrieved consumers must rely solely on the government to act to address a violation of the law. Even federal laws, such as ERISA, that allow individual consumers to bring a lawsuit to resolve certain disputes, have limited remedies to address a violation. ERISA does not generally allow monetary damages as a remedy.

Table comparing enforcement agencies and tools for different types of private health plans. DOL and Treasury enforce requirements for self-insured private employer-sponsored plans through investigations, lawsuits and penalties, including excise taxes of 0 per day per affected individual; individuals may also sue to recover benefits, although other remedies are limited. CMS enforces requirements for non-federal governmental employer-sponsored plans and may assess penalties of up to 0 per day per affected individual, but individuals have no federal private right of action. State insurance agencies have primary enforcement responsibility for individual and fully insured large and small group plans, using tools such as market conduct exams, penalties and other remedies. CMS serves as a federal fallback when a state does not substantially enforce federal requirements and may assess penalties of up to 0 per day per affected individual. DOL and IRS also have overlapping enforcement authority for fully insured group plans.

The federal fallback framework also applies to most of the requirements on health care providers and facilities that are now part of federal law. In 2020, Congress passed and President Trump signed the Consolidated Appropriations Act (CAA), which includes new protections on balanced billing (the No Surprises Act) and various provider rules regarding disclosure and transparency. States are expected to enforce these standards against providers, with CMS as the federal fallback. State health departments or state agencies that oversee provider and facility licensing and practice standards oversee these rules. CMS has surveyed states and entered into collaborative enforcement agreements with each state, including which CAA rules the state is prepared to enforce and which ones CMS will need to implement. CMS can assess a penalty of up to $10,000 per violation against a provider or facility for non-compliance.

Enforcement of other standards. Outside of the above federal fallback framework, each agency has its own separate enforcement mechanisms for the laws it implements alone. For instance, HHS has the authority to assess fines under HIPAA privacy rules for violations, but individuals harmed by a HIPAA violation do not have a private right of action under that law. Enforcement processes and remedies available under federal nondiscrimination requirements under the Civil Rights Act or the Americans with Disabilities Act vary, but some include monetary damages in the form of compensatory damages.

Who Regulates Private Health Insurance at the State Level, and What Are the Primary Enforcement Tools Used?

Copy link to Who Regulates Private Health Insurance at the State Level, and What Are the Primary Enforcement Tools Used?

The McCarran-Ferguson Act, enacted by Congress in 1945, clarified that states have the primary role in regulating the business of insurance. Although changes have since been made to that law, states have several mechanisms in place to regulate insurance. States license entities that offer private health coverage in a process that reviews the insurer’s finances, management, and business practices to ensure it can provide the coverage promised to enrollees. States also license the insurance agents and brokers in the state (see the section “What Is the Role of Health Insurance Brokers and Other Assisters?” for more information).

State insurance laws and regulations vary by state, though commonly include:

Table summarizing state responsibilities for regulating private health insurance. Financial standards include insurer capital, reserve, and investment requirements, as well as state financial examinations. Market conduct oversight includes claims handling, underwriting, marketing, advertising, and investigations of unfair trade and claims practices. States regulate insurance policy forms by setting standards for contract provisions, terminology, and policy approval. States also determine certain coverage requirements and mandated benefits, resulting in variation in covered services across states. Premium regulation includes review of proposed rate increases and, in some cases, stricter premium-rating rules than federal law requires. Consumer protection responsibilities include handling complaints, enforcing consumer protections, and providing independent external review processes for certain coverage disputes.

Most states require health plans to provide specific data that is included in the state’s all-payer claims databases (APCDs). These are state databases that include medical, pharmacy, and often dental claims, as well as eligibility and provider files collected from and aggregated across all private and public payers in a state. APCDs can provide states with a perspective on cost, service utilization, and quality of health care services across the full spectrum of payers in a state, which can be a tool in state efforts to control health care costs and promote value-based care.

Some states are also developing additional state-level regulations related to health plan network adequacy, health plan price transparency, public option plans, reinsurance programs, and more. These state-level regulations and protections do not apply to enrollees in self-insured plans offered by private employers (see the section “What is Private Health Insurance” for more information). However, these enrollees may have some of these protections through other federal laws and regulations.

State legislatures enact state insurance laws and typically grant regulatory authority to the state’s insurance regulator/commissioner. State enforcement mechanisms vary widely by state, regulation, state resources, and staffing capacity. Shifting political priorities at the state level can also influence enforcement priorities and actions. For example, state insurance agencies may ensure compliance with certain benefit mandates by primarily relying on complaints from consumers, consumer advocates, or health care providers to trigger a compliance review of the plan in question, while other state insurance agencies conduct periodic systematic reviews of all plans subject to the law or regulation.

What Is the Role of Health Insurance Brokers and ACA Consumer Assistance Programs?

Copy link to What Is the Role of Health Insurance Brokers and ACA Consumer Assistance Programs?

Navigating an increasingly complicated health coverage landscape has increased the focus on the availability and expertise of entities that assist purchasers of health coverage (consumers and employers). Assisters can include agents and brokers who are paid commissions from insurers, as well as consumer assistance programs created by the ACA, which are often publicly funded and nonprofit, who may provide similar assistance as agents and brokers, but also specialize in individuals transitioning in and out of public programs such as Medicaid or assisting those without insurance to find coverage.

Agents and brokers have long played a significant role in connecting individuals and employers to private health coverage by helping them understand health insurance options and costs. An “agent” typically represents a single insurer and provides information about that insurer’s coverage options. A “broker” is not aligned with any one insurer but could, in theory, place coverage from any insurer selling products in a state.

Agents and brokers assist individuals in choosing a qualified health plan on a health insurance Marketplace. Their role in Marketplace enrollment has grown over the years. In the 2024 plan year, 78% of ACA coverage was sold through health insurance agents compared to 43% in 2016. Web brokers, who facilitate plan selection online through Marketplace capabilities, have also played a large role in Marketplace enrollment.

Agents and brokers in the health insurance Marketplace have faced scrutiny for alleged fraudulent activity in recent years due to consumer reports of unauthorized enrollment and plan switches by agents and brokers. In response, CMS, under President Biden, began requiring additional steps to be taken before agents and brokers can make changes to a consumer’s HealthCare.gov enrollment, and hundreds of agents’ and brokers’ Marketplace agreements were suspended for reasonable suspicion of fraudulent activity. In an attempt to address Marketplace fraud, the Trump administration finalized a regulation in 2025 that, along with the 2025 budget reconciliation law, creates new administrative hurdles for consumers to enroll in Marketplace coverage and receive premium tax credits. These 2025 actions made few changes to broker oversight requirements for Marketplace plans. The Trump administration also reinstated many agents and brokers suspended in recent years, and federal indictments related to broker fraud for actions that allegedly occurred as far back as 2018 still await resolution.

Even before the creation of the Marketplaces, agents and brokers had been selling coverage in the individual and group insurance market, especially to small employers needing expertise in finding health insurance for their employees. Large employers also use agents and brokers, who often work for employee benefit consultants or brokerage firms and receive commissions (or, in some cases, a fixed fee) to find vendors to support their self-insured group health plan or for placing other forms of insurance that they provide or make available to employees as “voluntary” benefits.

Broker Compensation Reporting. Employer plans governed by ERISA must meet ERISA fiduciary standards. These standards prohibit plans from contracting with a “party-in-interest,” which is an entity that may have a conflict of interest because it is receiving compensation from a third party for activity it is doing for the employer plan. For instance, a benefits consultant may be helping an employer find a third-party administrator (TPA) for its group health plan, and the consultant is paid by the employer for their work but also gets a commission from the TPA if the employer decides to use its services. Employers are prohibited from entering into this type of transaction with the consultant unless they can show it was done in a “reasonable manner.”

Under rules added to ERISA by the CAA, one way an employer plan can demonstrate that its contract with a broker/consultant is reasonable is to show that it received information from the broker/consultant about the compensation the broker/consultant received from the TPA. Under these rules, an employer plan fiduciary violates ERISA if it does not receive from a broker or consultant information about the direct and indirect compensation the broker receives. Also, insurers offering individual insurance (on- and off-Marketplace) and those offering short-term limited-duration plans must disclose to enrollees and report to CMS any direct or indirect compensation they pay to agents and brokers for enrolling individuals in this coverage.

Consumer Assistance Programs. The ACA required the creation of other types of assisters to assist consumers with enrollment, plan selection, insurance problems, and, in some cases, post-enrollment support. These programs must provide impartial, no-cost help to consumers and cannot be affiliated with an insurance company.

Navigator programs, which are federally funded through grants, were created to raise public awareness and assist individuals in enrolling in qualified health plans as well as provide post-enrollment support. Navigators participate in trainings and are required to be knowledgeable in eligibility and enrollment rules and available QHP options, and maintain privacy and security standards. In 2025, CMS announced a 90% cut in Navigator funding, the largest funding cut since the program began. The current plan year funding of $100 million will be reduced to $10 million for 2026. These cuts come as enhanced Marketplace subsidies are set to expire at the end of 2025 and federal cuts to Medicaid begin to take effect in 2026, both of which could result in significant coverage losses.

Related assisters include Certified Application Counselors (CACs) who also assist consumers in resolving insurance issues and identifying the coverage option that best suits their needs. CACs, however, are not required to meet the same standards as Navigators or participate in all of the activities required of Navigators (e.g., providing post-enrollment assistance). In states using the federally-facilitated Marketplace (FFM), CACs are overseen by Certified Application Counselor Designated Organizations (CDOs), which are designated by CMS and include organizations such as community health centers, hospitals, and social services agencies. To serve as a CAC in an FFM state, the individual must be affiliated with a CDO and is typically a staff member or volunteer. CACs are not federally funded and instead rely primarily on outside non-profit organizations and foundations. 

The ACA also established Consumer Assistance Programs (CAPs) to assist consumers with insurance problems and identify their best options for health coverage. Unlike the Navigator program, which was specifically created to assist Marketplace, Medicaid, and CHIP consumers, CAP programs also assist consumers with employer-sponsored coverage and other types of coverage. The ACA provided an initial appropriation for CAPs, which 35 states and Washington, D.C., took advantage of, but CAP programs have received no federal funding since 2012. Many states have continued their CAP programs using their own funds, but others have discontinued their operations.

What is the Future Outlook for the Regulation of Health Insurance?

Copy link to What is the Future Outlook for the Regulation of Health Insurance?

2025 and beyond will likely see a retrenchment in regulation at the federal level that could impact the private coverage gains of the last decade. While states will still play a significant role in regulating private health insurance, the fragmented structure of private health care regulation and enforcement means that states alone are limited in what they can do to affect national change or influence private employer-based coverage, where most insured Americans under 65 get their coverage. The future regulatory outlook for private health coverage will be shaped by the following three key features:

Deregulation and Litigation. The Trump administration has put in motion, through several executive orders and other actions, deregulation across the health care sector. For example, a January 2025 executive order required that for every new regulation promulgated, federal agencies must identify at least ten existing regulations to repeal, which could impede future rulemaking. Another executive order required all federal agencies to coordinate with the president’s Department of Government Efficiency (DOGE) to review all regulations to make sure they are consistent with “law and Administration policy.” Using this executive order, the Trump administration has limited the enforcement of final regulations on mental health parity and short-term, limited-duration plans. Also in February 2025, President Trump issued an executive order that rescinded several executive orders issued by President Biden, including one aimed at strengthening the ACA.

These types of regulatory rescissions and a general deregulatory executive agenda, along with disruptions in agency structure and the personnel layoffs in the federal health care agencies, could have long-term impacts on private health care regulation. The outcome of court challenges to many of these deregulatory actions will determine future developments. In addition, changes in how courts review agency decisions—that is, the major decisions by the Supreme Court to limit agency discretion—could be a barrier to the Trump administration’s deregulation initiatives, as federal courts now have more power to second-guess policy decisions of the President. Look for attempts at codifying the Trump administration’s priorities through congressional action to get past any court barriers. Also, expect to see more actions from this administration through executive orders, voluntary industry agreements, and sub-regulatory guidance (e.g., advisory opinions that approve various industry arrangements). Changing enforcement priorities for federal agencies could leave patients looking to state and private mechanisms to get the protections written in federal law.

Technology Advancements. Expect wide-ranging recommendations from major stakeholders on which aspects of artificial intelligence (AI) and telehealth should be promoted and protected from federal regulation. The Trump administration has already announced its plans to speed up the development of AI and reduce regulation. With limited federal regulation anticipated during this administration, much of the future outlook for consumer protections will depend on the voluntary actions of industry and how transparent those activities are. For example, in July 2025, the Trump administration announced a new voluntary initiative aimed at enhancing health data interchange (known as “interoperability”) and expanding patients’ access to their own health data and reported that more than 60 companies had pledged to participate. Open questions about data privacy, security, and accuracy are key concerns as the details of this initiative and new apps are developed. Participation is optional, and the initiative does not create any new legally binding requirements for these companies. While the market for digital health care tools could benefit from the emphasis on AI and virtual care, without updated federal privacy and security rules, such as HIPAA, and nondiscrimination requirements, consumers may have to look to state regulation for these protections. Additionally, new, expensive gene therapies and blockbuster medications will likely increase the overall cost of health care and could also challenge policymakers to rethink existing reimbursement structures and government intervention in pricing.

Consumer Choice. Look for policy shifts from consumer assistance and protection to efforts to broaden the health coverage choices available to consumers to include those that may not meet all of the ACA’s consumer protection requirements. The emphasis on “choice” will likely include efforts to encourage consumers to use tax-advantaged accounts such as health savings accounts, which can be used to set aside funds to purchase an increasing variety of items and pay for health care services provided via direct primary care arrangements and telehealth before the deductible applies. Policy debates on whether low-income individuals and those with chronic illnesses are best served by these account-based models are also possible.

Resources

Copy link to Resources

Citation

Copy link to Citation

Pestaina, K., Wallace, R., & Long, M., The Regulation of Private Health Insurance. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-the-regulation-of-private-health-insurance/ (date accessed).

The U.S. Government and Global Health

Table of Contents

Introduction

Copy link to Introduction

While there is currently no standard, agreed-upon definition of global health, the National Academy of Medicine (formerly Institute of Medicine) defines global health as having “the goal of improving health for all people in all nations by promoting wellness and eliminating avoidable diseases, disabilities, and deaths.” A key dimension of global health is an emphasis on addressing inequities in health status between rich and poor countries and also for those who are most marginalized within countries, as well as a recognition that the health of people around the world is highly interconnected, with domestic and foreign health inextricably linked. 

The U.S. government has long been the largest donor to and implementer of global health programs in the world. These efforts have aimed to help improve the health of people in low- and middle-income countries while also contributing to broader U.S. global development goals, foreign policy priorities, and national security concerns, including helping safeguard the health of Americans. These efforts began decades ago and saw major expansion in the early part of the current century with the creation of the President’s Emergency Plan for AIDS Relief (PEPFAR) and other programs. Since the beginning of the second Trump administration, however, the U.S. global health response has undergone significant change, disruption, and retraction, and the global health landscape has been altered in fundamental ways. This has included, as part of a major review of U.S. foreign aid, the dissolution of the U.S. Agency for International Development (USAID), the main implementing agency for U.S. global health programs, the elimination of numerous programs and projects, and the transition of remaining programs to the State Department.  As part of its review, the administration is seeking to assess whether U.S. foreign aid programs are aligned with U.S. national interests.

What Is the U.S. Role in Global Health?

Copy link to What Is the U.S. Role in Global Health?

Historically, the U.S. role in global health is multifaceted and includes a broad range of activities. Its primary roles are as a supporter of bilateral (i.e., country-to-country) efforts, directly funding implementation of global health efforts in partner countries, and as a donor to multilateral health institutions (i.e., international organizations that pool support from multiple countries for one or more areas of global health). The U.S. also engages in global health diplomacy through its relationships with other governments, multilateral institutions, non-governmental organizations, and the private sector. Specifically, the U.S. government:

  • acts as a donor by providing financial and other health-related development assistance (e.g., commodities, like contraceptives or bed nets for protection from disease-carrying mosquitoes) to low- and middle-income countries;
  • operates programs and delivers health services;
  • provides technical assistance and other capacity-building support;
  • participates in major international health organizations and coordinates health efforts with other stakeholders through global health diplomacy;
  • conducts research;
  • supports international responses to disasters and other emergencies; and
  • partners with governments, non-governmental groups, and the private sector (Figure 1).

U.S. global health activities have targeted a variety of issues and used different intervention approaches such as:

  • Health services and systems strengthening: improving basic and essential health services, systems, and infrastructure;
  • Disease detection and response: supporting surveillance, prevention, and treatment of diseases, including both infectious (e.g., HIV, TB, malaria) and non-communicable diseases (e.g., cardiovascular disease, cancer);
  • Population and maternal/child health: promoting maternal health; reproductive health and family planning; child nutrition, immunization, and other child survival interventions;
  • Nutrition, water, and environmental health: providing non-emergency food aid and supporting dietary supplementation and food security; clean/safe water and sanitation; mitigation of environmental hazards; and
  • Research and development: investigating and developing new technologies, interventions, and strategies, including vaccines, medicines, and diagnostics.

What Are the Major Global Health Program Areas the U.S. Supports?

Copy link to What Are the Major Global Health Program Areas the U.S. Supports?

While the U.S. government’s involvement in global health currently faces an uncertain future – with a more limited scope, the dissolution of USAID, and cancelation of numerous U.S.-supported global health projects, as the Trump administration seeks to reorganize foreign aid more broadly –  the U.S. has historically supported global health through a wide array of bilateral and multilateral global health programs in countries around the world including:

HIV/PEPFAR

While the U.S. first provided funding to address the emerging global HIV epidemic in 1986, U.S. funding and attention for these efforts has grown significantly in the last two decades, particularly following President George W. Bush’s 2003 announcement of the President’s Emergency Plan for AIDS Relief (PEPFAR), the coordinated U.S. government response to global HIV. Now the largest commitment by any nation devoted to a single disease, the launch of PEPFAR led to substantially increased U.S. support for HIV prevention, treatment, and care efforts, as well as U.S. contributions to multilateral entities, including the Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund), the Joint United Nations Programme on HIV/AIDS (UNAIDS), and the International AIDS Vaccine Initiative (IAVI).  PEPFAR, which is housed in the Department of State, has been credited with saving 26 million lives and contributing to broader health, educational, and economic gains.  Currently, PEPFAR faces significant change. While U.S. policymakers had been increasingly looking at when and how to transition PEPFAR services and financing to country governments, the current Trump administration has sought to narrow PEPFAR’s scope and significantly accelerate this timeline. See the “Status of PEPFAR” fact sheet for more information.

Tuberculosis (TB)

Since the 1998 launch of USAID’s global TB control program, the U.S. response to global TB has expanded, particularly after 2003 when PEPFAR highlighted the U.S. government’s commitment to addressing TB. Prior to the current Trump administration, these efforts focused on diagnosis, treatment, and control of TB (including multi-drug-resistant and extensively drug-resistant TB, or MDR/XDR TB) as well as on research. The U.S. was also a donor to the Global Drug Facility of the Stop TB Partnership.  With the dissolution of USAID, remaining TB programming has been moved to the State Department and its scope has been reduced. See the “Status of U.S. Global Tuberculosis Efforts” fact sheet for more information.

Malaria/PMI

Engaged in malaria work since the 1950s, the U.S. supported expanded malaria efforts in low- and middle-income countries through the President’s Malaria Initiative (PMI), launched in 2005 and housed at and managed by USAID, as well as through research and other activities. PMI programs centered on expanding coverage of six key high-impact interventions to control or eliminate malaria, which included: diagnosis of malaria and treatment with artemisinin-based combination therapies (ACTs), entomological monitoring, intermittent preventive treatment in pregnancy (IPTp), indoor residual spraying (IRS) with insecticides, insecticide-treated mosquito nets (ITNs), and seasonal malaria chemoprevention (SMC). The U.S. has also supported the RBM Partnership to End Malaria.  Under the current administration, remaining PMI programming has been moved into the State Department. See the “Status of the President’s Malaria Initiative (PMI)” fact sheet for more information.

Maternal and Child Health (MCH)

Involved in efforts to improve MCH since the 1960s,  U.S. global MCH activities, which had been housed at and managed by USAID, aimed to bring to scale a range of high-impact interventions that mitigate maternal, newborn, and under-five deaths; prevent and address the indirect causes of such deaths (such as HIV, TB, and malaria); strengthen integration of maternal health services with family planning; improve equity of access to and use of services by vulnerable populations; and strengthen health systems. The U.S. has also been a donor to global organizations and initiatives addressing MCH, such as Gavi, the Vaccine Alliance, the United Nations Children’s Fund (UNICEF), and the Global Polio Eradication Initiative (GPEI).Under the current administration, remaining MCH programming has been moved into the State Department. See the “Status of U.S. Global Maternal and Child Health Efforts” fact sheet for more information.

Nutrition

For more than 40 years, the U.S. had been involved in nutrition efforts in low- and middle-income countries that aimed to prevent undernutrition through support for effective interventions, such as nutrition education, nutrition during pregnancy, exclusive breastfeeding, and micronutrient supplementation. Housed at and managed by USAID, U.S. global nutrition efforts were coordinated with the U.S. Feed the Future Initiative (FtF, launched in 2009), which aimed to address global hunger and food security. Currently, remaining nutrition programming has been moved to the State Department. See the “Status of U.S. Global Maternal and Child Health Efforts” fact sheet for more information.

Family Planning and Reproductive Health (FP/RH)

Engaged since the 1960s in international research on family planning and population issues as well as other FP/RH efforts (including the purchase and distribution of contraceptives in developing countries),  U.S. global FP/RH activities were designed to decrease the risk of unintended pregnancies and maternal and child mortality through effective interventions, including contraception, counseling, and post-abortion care. The U.S. also provided funding to global organizations addressing FP/RH, such as the United Nations Population Fund (UNFPA), though in some years, funding for UNFPA was withheld. The current administration has moved to end U.S. bilateral and multilateral support for family planning efforts. See the “Status of U.S. Family Planning and Reproductive Health Efforts” fact sheet for more information

Neglected Tropical Diseases (NTDs)

Having historically worked on addressing NTDs through research and surveillance, attention to and funding for U.S. global NTD efforts increased markedly in 2006 with the launch of the USAID NTD Program and the subsequent announcement of expanded efforts across the U.S. government in 2008. These efforts had focused on five NTDs (soil-transmitted helminths,  lymphatic filariasis or elephantiasis, onchocerciasis or river blindness, schistosomiasis or snail fever, and trachoma) that are responsible for the overwhelming majority of the NTD burden but can be controlled and even eliminated with low-cost and effective interventions, such as an integrated control approach targeting multiple NTDs simultaneously through mass drug administration (MDA). The future of NTD efforts is uncertain amid the current Trump administration’s foreign aid freeze and dissolution of USAID.

Global Health Security (GHS)

While the U.S. has supported global health security work for more than two decades, its involvement has expanded over time, with attention to these efforts growing significantly due to the COVID-19 pandemic. These efforts aimed to reduce the threat of emerging and re-emerging diseases by supporting preparedness, detection, and response capabilities worldwide. The U.S. had also played a key role in the development and 2014 launch of the “Global Health Security Agenda (GHSA).” Through this international partnership that now involves more than 70 countries and international organizations, the U.S. worked to help countries make measurable improvements in their GHS capabilities. The U.S. had also been a donor to the new Pandemic Fund, which seeks to provide sustained financing to help countries build their capacity to prevent, prepare for, and respond to epidemics and pandemics.  While the first U.S. global health security strategy had been developed by the first Trump administration, the current Trump administration has withdrawn this strategy, eliminated several global health security positions and some offices, and withdrawn from U.S. engagement in key international efforts. See the “Status of Global Health Security/Pandemic Preparedness” fact sheet for more information.

How Much Funding Does the U.S. Provide for Global Health?

Copy link to How Much Funding Does the U.S. Provide for Global Health?

In FY 2025, U.S. funding appropriated by Congress for global health totaled $12.4 billion. While this funding has been appropriated to federal agencies, the current administration has withheld much of it from programming and sought to formally rescind (cancel) more than $1 billion in funding for global health, including some PEPFAR funding (Congress voted to amend the rescission package, reducing that amount to $500 million, and exempting PEPFAR and some other global health programs from cuts).  As such, funding amounts presented here for the current fiscal year may not reflect actual obligations or outlays of U.S. support. There is ongoing litigation federal court regarding these actions.

As Figure 2shows, U.S. appropriations for global health have grown significantly since the early 2000s, in large part due to funding for initiatives such as PEPFAR and PMI, but with spikes in some years due to emergency or supplemental funding for disease outbreaks such as Ebola, Zika, and COVID-19. Funding reached its highest level to date in FY 2021, largely due to the U.S. global response to the COVID-19 pandemic.

Although a large majority of the American public overestimates the share of the federal budget that is spent on foreign aid (with nearly half believing that the share is greater than 20%), U.S. foreign aid actually accounts for 1% or less of the federal budget, with U.S. funding for global health—which is part of the foreign affairs budget—accounting for an even smaller share.

U.S. Global Health Funding (in billions), FY 2006 - FY 2025

U.S. Global Health Funding by Program Area

Looking across funding for the major global health program areas since FY 2006, most U.S. global health funding over time has been directed to HIV programs, accounting for approximately 50% of U.S. global health funding in most years (Figure 3). The Global Fund accounted for the next largest share over the period, followed by MCH and malaria. More recently, the U.S. has emphasized global health security more, with funding for these efforts increasing considerably during the COVID-19 pandemic and afterward. Consistent with this trend, most funding was provided to HIV efforts ($5.4 billion or 44%), followed by the Global Fund ($1.7 billion or 13%) and maternal and child health and global health security (both $1.3 billion or 10%) in FY 2025 (Figure 4).

Distribution of U.S. Global Health Funding, by Program Area, FY 2006 - FY 2025
U.S. Global Health Funding (in millions), by Program Area , FY 2025

Bilateral vs. Multilateral Aid

Most U.S. global health funding is provided bilaterally – that is, funding provided by the U.S. directly to or on behalf of a recipient country or region. In FY 2025, about 80% of the U.S. global health budget was provided through bilateral programs. The remainder (about 20%) is provided multilaterally through U.S. contributions to international institutions and organizations (see “What Multilateral Health Organizations Are Supported by the U.S.?”).

Which U.S. Agencies Are Involved in Carrying Out Efforts in These Program Areas?

Copy link to Which U.S. Agencies Are Involved in Carrying Out Efforts in These Program Areas?

Historically, the U.S. government’s engagement in global health has been carried out and overseen by multiple executive branch departments and agencies and the legislative branch, including several congressional committees (Figure 5). The current administration has made significant changes to this infrastructure. See the “Proposed Reorganization of U.S. Global Health Programs” fact sheet for more information.

Executive Branch

In general, U.S. global health engagement has developed within two main structures of the Executive Branch of government: the foreign assistance structure, which is predominantly global development-oriented and has close links to foreign policy; and the public health structure, which has its roots in disease prevention, control, and surveillance efforts.

Most funding for and oversight of U.S. global health resides within the foreign assistance structure, including:

  • Department of State (State): Established in 1789, the Department of State is the Cabinet-level foreign affairs agency of the United States. It advances U.S. objectives and interests worldwide through its primary role in developing and implementing the President’s foreign policy. Prior to the current Trump administration, it also provided policy direction to USAID, the lead federal agency for development assistance. The Trump administration has dissolved USAID and moved remaining global health activities into the Department of State. The Department of State’s Bureau for Global Health Security and Diplomacy (GHSD) coordinates the Department’s work on global health security, including HIV, and houses PEPFAR.
  • U.S. Agency for International Development (USAID): Established in 1961, USAID was an independent U.S. federal government agency that received overall foreign policy guidance from the Secretary of State. Its role was to support long-term and broad-based economic growth in countries and advance U.S. foreign policy objectives by supporting activities through each of its programmatic functional bureaus (e.g., Bureau for Global Health) and regional bureaus. Most USAID global health programs had been coordinated through the Bureau for Global Health, including HIV and other infectious diseases, MCH, nutrition, FP/RH, NTDs, and global health security. USAID has now been dissolved by the current administration.  
  • Millennium Challenge Corporation (MCC): Established in 2004, MCC administers the Millennium Challenge Account (MCA), a U.S. government initiative providing development assistance to eligible countries to promote economic growth and reduce poverty in low- and middle-income countries. Although MCC supports several health-related programs, health is not the main focus or purpose of its work; its design is intended to link MCC contributions for development assistance (to reduce poverty through support for economic growth) to greater responsibility by low- and middle-income countries for successfully attaining certain governance and development benchmarks. The current Trump administration had sought to close down the agency but ultimately did not do so.

Agencies within the public health structure operate global health programs directly or in conjunction with foreign assistance agencies. They are represented most prominently by several agencies within the Department of Health and Human Services (HHS), including:

  • Office of Global Affairs (OGA): OGA’s primary function is global health diplomacy – particularly coordinating and maintaining engagement across HHS and the U.S. government with foreign governments and ministries of health, multilateral organizations, civil society groups, and the private sector – exchanging best practices and sharing technical knowledge to advance U.S. global health priorities and research.
  • Centers for Disease Control and Prevention (CDC): With a long history of working on international health issues, prior to the current Trump administration, CDC focused on disease control and prevention and health promotion through operations, development assistance, basic and field research, technical assistance, training/exchanges, and capacity building. The current administration has eliminated many of the staff working on these issues and sought to eliminate the CDC’s global health center.
  • National Institutes of Health (NIH): One of the world’s leading research entities on global health, NIH conducts biomedical and behavioral science research on diseases and disorders to enhance diagnosis, prevention, and treatment and provides technical assistance and training. Prior to the current Trump administration, all 27 of the agency’s institutes and centers engaged in global health activities, but these activities are already being curtailed or eliminated.
  • Food & Drug Administration (FDA): The FDA screens pharmaceutical and biological products for safety and efficacy and helps oversee the safety of the U.S. food supply.
  • Health Resources and Services Administration (HRSA): HRSA builds human and organizational capacity and promotes health systems strengthening to deliver care in PEPFAR countries.

In addition to the foreign assistance and public health service agencies, other departments and agencies involved in global health have included the Department of Defense (DoD), the Department of Agriculture (USDA), the Peace Corps, the Environmental Protection Agency (EPA), the Department of Homeland Security (DHS), the Department of Labor (DoL), the Department of Commerce (Commerce), the Office of the U.S. Trade Representative (USTR), and the National Security Council (NSC). The NSC, which sits within the White House, plays a significant role across the U.S. government, as it is responsible for coordinating and reviewing the U.S. strategy and activities related to global health security, including its international response. However, the administration has eliminated many of the staff working on these issues, and is no longer operating the White House Office of Pandemic Preparedness and Response (OPPR), which had been responsible for domestic policy coordination related to health security.

Legislative Branch

The U.S. Congress introduces, considers, and passes global health-related legislation; oversees global health efforts, specifying how funds for these programs are to be (and not to be) spent; authorizes and appropriates funding; and confirms presidential appointees to key U.S. global health positions. Major committees of the House of Representatives (House) and Senate with jurisdiction over global health efforts include: the House Committee on Foreign Affairs, Senate Committee on Foreign Relations, House Committee on Energy and Commerce, Senate Committee on Health, Education, Labor, and Pensions, and the Senate and House Appropriations Committees.

The U.S. global health response has been defined by numerous governing statutes, authorities, and policy decisions. For instance, the legislation that created PEPFAR in 2003 and its subsequent reauthorizations in 2008, 2013, 2018, and 2024 are key statutes of U.S. global health policy, as they govern its bilateral HIV response, bilateral assistance for TB and malaria, and participation in the Global Fund. Other statutory requirements that shape the implementation and scope of U.S. global health activities are those governing U.S. global FP/RH efforts, such as those directing how U.S. funds may not be spent. For instance, the Helms Amendment (1973) prohibits the use of foreign assistance to pay for the performance of abortion as a method of family planning or to motivate or coerce any person to practice abortion. The Kemp-Kasten Amendment (1985) prohibits funding any organization or program, as determined by the President, that supports or participates in the management of a program of coercive abortion or involuntary sterilization (it has been invoked at times to restrict funding to UNFPA).

While Congress has authority over many aspects of global health, the current administration has taken several actions without its direct consent (such as eliminating USAID and withholding Congressionally-directed appropriations), and has questioned the extent of Congressional authority in these areas. It is unclear if Congress will act on these issues and some of these questions are being litigated in federal court.

Where Do U.S. Bilateral Global Health Programs Operate?

Copy link to Where Do U.S. Bilateral Global Health Programs Operate?

Prior to the current Trump administration, the U.S. provided bilateral support for U.S. global health programs in almost 80 countries, with additional countries reached through U.S. regional global health programs and U.S. contributions to multilateral organizations. Multiple factors determined where the U.S. channeled its global health support. While more U.S. support was generally directed to countries facing a higher burden of disease, it was also influenced by factors such as the presence of willing and able partner governments, a history of positive relations and goodwill with host countries, strategic and national security priorities, and funding and personnel availability. The majority of countries receiving U.S. bilateral support for global health (“partner countries”) were located in sub-Saharan Africa (35 countries), followed by the Western Hemisphere (14 countries), East Asia and Oceania (11 countries), South and Central Asia (9 countries), Europe and Eurasia (4 countries), and Middle East and North Africa (4 countries) (Figure 5). Most U.S. bilateral support for global health programs was provided in sub-Saharan Africa (84%) (Figure 6). Furthermore, the top 10 country recipients of U.S. global health funding, representing 59% of U.S. bilateral support for global health, were all in this region (Figure 7).

Countries Where the U.S. Operates Global Health Programs, by Region, FY 2023
U.S. Global Health Funding, by Region, FY 2023
Top 10 Recipient Countries of U.S. Global Health Funding, FY 2023

The U.S. typically operated more than one health program (HIV, TB, malaria, etc.) in each partner country. While in most countries, the U.S. operated programs in four or fewer global health areas, this number was generally higher in countries in sub-Saharan Africa (five or more).

What Multilateral Health Organizations Are Supported by the U.S.?

Copy link to What Multilateral Health Organizations Are Supported by the U.S.?

In addition to its bilateral programs, the U.S. has a long history of engagement with multilateral health organizations and international institutions, beginning with its role in the development of the first such organizations, including the Pan-American Health Organization (PAHO) in the early 1900s and the World Health Organization (WHO) a few decades later. This involvement continued with, for example, the Global Fund (which the U.S. helped to launch in 2001), Gavi (launched in 2000), the GHSA (which the U.S. played a key role in developing and launching in 2014), and the Pandemic Fund (launched in 2022). Prior to the current Trump administration – which is carrying out a review of its engagement in international organization to determine the future of U.S. multilateral participation and support – U.S. support for multilateral global health efforts has taken various forms, including:

  • Funding. The U.S. has often been the largest or one of the largest donors to multilateral health efforts, funding core (generally used to support essential functions and operations) and voluntary (used for specific projects or initiatives the U.S. seeks to support) contributions. About a fifth (19%) of U.S. global health funding supported U.S. contributions to multilateral health organizations (Figure 8). However, some global health support to multilateral organizations has already been reduced or eliminated by the current Trump administration, such as funding and engagement in the World Health Organization, UNFPA, and the Pandemic Fund.
  • Governance. The U.S. has been active in the governance structures that oversee multilateral global health organizations and initiatives, including holding permanent or rotating seats on many of their boards.
  • Technical assistance. The U.S. has offered technical assistance in support of grants to partner countries, providing additional staff capacity to international organizations (by detailing U.S. government employees to these organizations for periods of time).
  • Standard setting. The U.S. has engaged in standard-setting, weighing in on global plans, treaties, and agreements to respond to a range of health issues as they are developed and considered for approval by the larger body.
U.S. Multilateral Global Health Funding (in millions), FY 2025

The U.S. has engaged with a number of multilateral global health organizations, including health-focused specialty agencies of the United Nations (U.N.) and international financing mechanisms for global health. Key among these are eight to which Congress specifically directs funding (though the U.S. also reaches other multilateral health institutions without direct Congressional appropriations but rather through general support), of which the U.S. has been the top contributor to five (the Global Fund, PAHO, UNAIDS, UNICEF, and WHO):

U.N. Agencies

  • World Health Organization (WHO): WHO, created in 1948, is the directing and coordinating authority for health within the U.N. system. WHO provides international leadership on global health matters, shaping the health research agenda, setting norms and standards, providing technical support to countries, and monitoring and assessing health trends. The U.S. has been involved in WHO since its creation, providing financial and technical support as well as participating in its governance structure. However, President Trump announced on the first day of his second term that the U.S. would withdraw as a member of WHO and halt funding to the organization.
  • Pan American Health Organization (PAHO): PAHO is the oldest international health agency, founded originally as the International Sanitary Bureau in 1902. The U.S. joined PAHO as a member state in 1925. PAHO, the specialized international health agency for the Americas, “works with countries throughout the region to improve and protect people's health” and serves as the WHO Regional Office for the Americas and as the health organization of the inter-American System.
  • Joint United Nations Programme on HIV/AIDS (UNAIDS): UNAIDS, created in 1996 as the successor organization to the WHO Global Programme on AIDS (GPA), is the leading global organization for addressing HIV/AIDS. Coordinating efforts across the U.N. system, it is made up of 11 U.N. co-sponsors and guided by a Programme Coordinating Board (PCB), which is a subset of its co-sponsors and government representatives. The U.S. currently serves on the PCB.
  • United Nations Children’s Fund (UNICEF): UNICEF, created in 1946, aims to improve the lives of children, particularly the most disadvantaged children and adolescents, and is one of the largest purchasers of vaccines worldwide. The U.S. was a founding member that same year.
  • United Nations Population Fund (UNFPA): UNFPA, created in 1969, is the largest purchaser and distributor of contraceptives worldwide. While the U.S. helped to found UNFPA and was a leading supporter for many years, its support has fluctuated significantly and sometimes been withheld entirely over the years, due to ongoing U.S. political debates about abortion. The Trump administration has announced that it is withholding funding from UNFPA.

Non-U.N. Financing Mechanisms

  • Gavi, the Vaccine Alliance (Gavi): Gavi, created in 2000, is a public-private partnership that aims to increase access to immunization in poor countries. The U.S. has been involved in Gavi since its creation through contributions, participation in Gavi’s governance, and technical assistance. The U.S. is the second largest donor to Gavi’s core programs and the top donor to Gavi’s COVAX Advance Market Commitment (COVAX AMC), a financial mechanism within COVAX that supports low- and middle-income countries through procurement and distribution of COVID-19 vaccines.
  • Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund): The Global Fund, created in 2001, is an independent multilateral financing entity that supports HIV, TB, and malaria programs in low- and middle-income countries. The U.S. was involved in creating the Global Fund and maintains a permanent seat on its Board. U.S. contributions and those of other donors are pooled and then provided by the Global Fund to country-driven projects based on technical merit and need.
  • TB Global Drug Facility: The Global Drug Facility, created in 2001, is a financing mechanism of the Stop TB Partnership; it provides grants to countries for TB drugs.

U.S. support for multilateral institutions overall has fluctuated over time, reflecting, in part, changing U.S. leadership views on the relative value of bilateralism versus multilateralism. As a result, U.S. engagement in and contributions to specific multilateral health organizations and institutions may change over time. For example, the U.S. under the first Trump administration did not participate in the partnership to create  COVAX (an international partnership led by the Coalition for Epidemic Preparedness Innovations [CEPI], Gavi, and WHO) to facilitate greater global access to the COVID-19 vaccine, although Congress did provide $4 billion in emergency funding to Gavi in support of COVID-19 vaccine access. Under the Biden administration, the U.S. joined the COVAX partnership.

Multilateral initiatives complement U.S. bilateral global health efforts, helping make progress toward U.S. goals in various program areas. In some cases, U.S. multilateral global health support allows the U.S. to reach a larger number of countries; it also may help to leverage additional funding and provide opportunities for improved coordination and technical consultations. Additionally, U.S. policies related to funding can greatly influence other financial support for multilaterals. For instance, since U.S. law has required that the U.S. contribution to the Global Fund cannot exceed 33% of total contributions from all donors, the U.S. contribution has leveraged other donor contributions; in effect, this requirement encouraged increased support from other donors and prevented the U.S. from becoming the predominant donor to the Global Fund.

How Does the U.S. Compare to Other Donors of International Health Assistance?

Copy link to How Does the U.S. Compare to Other Donors of International Health Assistance?

The U.S. has been the largest donor to global health, providing over 40% of all international health assistance among major donor governments (Figure 9).

U.S. was the Largest Donor Government of International Health Assistance in 2023

In addition, the U.S. has historically devoted more of its foreign assistance to health than any other donor government, contributing over a quarter of its foreign assistance to global health in 2023 (Figure 10). The U.S. has also been the largest government donor to several specific global health areas, including HIV and family planning. Currently, however, the Trump administration is withholding global health funds in several areas and actual spending levels are still unknown.

Donor Governments with the Largest Share of Development Assistance Directed to International Health in 2023

Future Outlook

Copy link to Future Outlook

While the U.S. has been engaged in international health activities for over a century and has historically been the largest funder and implementer of global health programs worldwide, it is currently undergoing a fundamental shift, with a significantly reduced footprint and role.  Given the prominence of the U.S. in global health, these actions have and will influence the larger global health ecosystem and the health of those in low and middle income countries. Among the key issues to watch are:

  • The future direction of U.S. leadership in and degree of commitment to global health as the Trump administration reorganizes foreign assistance more broadly and seeks to permanently alter the U.S. role.
  • The status of U.S. funding for global health, particularly given the interplay between Congress and the administration on whether and how that funding gets spent and ongoing litigation in this area.
  • The ability of global health implementers to continue to deliver services to those who need them, given their loss of funding and future uncertainty.
  • The future role of multilateral institutions in global health, as the U.S. bilateral role is reduced, but also its support for multilateral health efforts remains unclear.
  • Whether other donors (governments, foundations, the private sector) will help to fill some of the gaps left by the U.S.
  • Whether the nations that have been recipients of U.S. global health support will increase their own financing and delivery of health services to their populations.

Resources

Copy link to Resources

Citation

Copy link to Citation

Oum, S., Moss, K., & Kates, J., The U.S. Government and Global Health. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-the-u-s-government-and-global-health/ (date accessed).

LGBTQ+ Health Policy

Table of Contents

Introduction

Copy link to Introduction

The share of individuals identifying as LGBTQ+ in the United States has increased over time, rising from just 4% in 2012 to 8% in 2023. In addition, support for same-sex marriage has also grown (27% in 1996 v. 69% as of 2024) and fewer believe there should be less acceptance for LGBTQ+ people (26% in 2001 v. 8% in 2020). Increases in identity and acceptance have been punctuated by several Supreme Court decisions providing new civil rights for LGBTQ+ people. Still, widespread stigma and discrimination persist for many LGBTQ+ people, including in health care as well as across a range of social institutions. These experiences can fuel significant health care disparities among LGBTQ+ people, challenging well-being and affecting health outcomes. Further, LGBTQ+ rights and health care access have become increasingly politicized at the federal and state levels, especially when it comes to young people.

All people’s health and health care experiences are informed by the socioeconomic context in which they live, including the policy environment. Federal and state policy can facilitate or impede access to health care for LGBTQ+ people. At the federal level, there have been both expansions as well as restrictions in protections and access over time and across presidential administrations, including the second Trump administration. Starting on the first day of his second term, President Trump began to issue numerous executive actions, several of which directly address or affect health programs, efforts, or policies designed to meet the health needs of LGBTQ+ people. These include actions that seek to limit data collection, lessen civil rights protections, restrict access to care, and remove acknowledgement of diverse sexual and gender identities. At the state level, there has been a rapid increase in the number of laws and policies impacting LGBTQ+ people’s health, especially, though not exclusively, that of young people. An increasing number of legal challenges to federal and state laws may ultimately decide access to care and the extent to which protections remain. This chapter provides an overview of LGBTQ+ people’s identities, experiences with health and health care, and the related health policy landscape.

A Note on Language

Throughout this chapter, whenever possible, we use the term LGBTQ+ to represent the full spectrum of non-heterosexual, non-cisgender people. Additionally, people who are asexual, questioning, or intersex are sometimes included under the LGBTQ+ umbrella. However, at times, the reader may encounter differences in terminology (e.g., LGBT, LGB, etc.). In these circumstances, we use language to reflect the specific data being cited. It is important to note that the language used to describe LGBTQ+ people has evolved considerably over time and will likely continue to do so.

Sex, Sexual Orientation, and Gender Identity

Copy link to Sex, Sexual Orientation, and Gender Identity

The concepts of sex, gender, and sexual orientation are discreet. However, they are often thought of as interrelated and dependent on one another, though their actual relationship is more diverse and complex:

  • Sex is often described as one’s biological categorization of being male or female based on anatomical, hormonal, and genetic factors. At birth, individuals are typically assigned a sex based on external genitalia. While sex is often thought of as a binary, as many as 1.7% of the population has been estimated to have some intersex trait, with population estimates of people with anatomical variations being lower (less than 0.5% of the population).
  • Gender identity is an individual’s sense or experience of being male, female, transgender (trans), non-binary, gender non-conforming, or something else. Gender identity may or may not align with the sex that was assigned at birth. Gender expression is the public expression of gender identity, which may occur through attire, body characteristics (e.g., hair), voice, etc. Gender expression may or may not align with traditional assumptions related to sex or gender identity.
  • Sexual orientation refers to emotional, romantic or sexual attraction to other people, often in relationship to one’s own sex and/or gender identity.

While many people and institutions historically considered these three concepts to be inseparably linked and linear (e.g., assigned the male sex at birth, identifies as male, and is attracted to women), there is wide variation in how these concepts relate, and they can be dynamic over time.

Who Are LGBTQ+ People?

Copy link to Who Are LGBTQ+ People?

It is estimated that 9.3% of U.S. adults identify as LGBTQ+, as of 2024, nearly triple the share in 2012 (3.5%), and LGBTQ+ identity is expected to continue to increase over time. This increase may reflect changes in behavior and desire, and an increased willingness to self-identify and disclose as societal acceptance has grown. Indeed, these two factors are likely interrelated. LGBTQ+ identity is strongly associated with age; younger generations self-identify at higher rates than older generations (23% of those aged 18-27 identify as LGBTQ+ compared to just 2% among those aged 79 and older). In addition, as of 2023, about 1 in 4 high school students identifies as LGBQ+. As the LGBTQ+ population ages and new generations identify at higher rates, it is expected that the share of adults who identify as LGBTQ+ will increase as well.

As such, the LGBTQ+ population is younger than the U.S. population overall. Almost half (47%) of LGBT adults are under age 30, compared to 18% of non-LGBT adults. Just 6% are 65 or older, compared to nearly one-quarter (24%) of non-LGBT adults (see Figure 1). LGBT adults are also more likely to have lower incomes and be living on less than $40,000 per year than non-LGBT adults (42% v. 33%), which may reflect their lower age. (See Table 1.)

Demographics of LGBT and Non-LGBT Adults

Within the LGBTQ+ community, identity is complex and multifaceted. Among adults who identify as LGBTQ+, the majority identify as bisexual (56%), a finding driven by younger adults, followed by gay (21%), and lesbian (15%). Smaller shares identify as transgender (14%), pansexual (1%), or in some other way (5%).

It is estimated that over 2.8 million adults and youth (over 13 years old) living in the U.S. identify as transgender or trans, which translates to 1% of all those 13 and older. A 2023 KFF/Washington Post Survey of a nationally representative sample of transgender adults in the U.S shows the trans adult population is younger than the larger cisgender adult population, with the majority of trans adults under the age of 35, echoing trends seen in the larger LGBTQ+ population. Additionally, most (70%) trans adults identify as lesbian, gay, or bisexual, compared to one in ten cisgender adults. Trans adults and cisgender adults do not notably differ when it comes to race and ethnicity or income. (See Table 2.)

A table shows demographic differences between transgender and cisgender adults. Transgender adults are younger than cisgender adults with just over half being 18-34 years old compared to just over a quarter of cisgender adults. They are also more likely to identify as lesbian, gay or bisexual (70% vs. 8%). There are not major differences between the groups by income or race/ethnicity.

Most trans adults, or about 6 in 10, describe themselves as “trans, gender non-conforming” or “trans, nonbinary,” while smaller shares say they would describe themselves as a “trans woman” (22%) or a “trans man” (12%). (See Figure 1.)

Stacked horizontal bar chart shows responses from trans adults to the question, “Which of the following best describes how you think of yourself?” The largest share, 40%, identify as “Trans, nonbinary.” Another 22% identify as “Trans, gender non-conforming,” and 22% identify as a “Trans woman.” About 12% identify as a “Trans man.” A small remaining share identify “Some other way.”

In addition to sexual orientation and gender identity, the lives of people who are LGBTQ+ are also shaped and informed by a range of other intersectional sociodemographic factors, including race/ethnicity, income, geography, educational opportunities, language, citizenship status, disability status, and other variables, which, together, affect health access and outcomes in both positive and negative ways.

Data Collection

Having an understanding of who the LGBTQ+ community is, what challenges they face, what their health needs are, and how those differ from non-LGBTQ+ people allows policymakers, providers, and others to better meet the community’s needs. While the share of people who identify as LGBTQ+ has increased over time, the community is still a relatively small share of the overall population (approximately 8%). This makes representative data collection more difficult, particularly for sub-group analysis, since obtaining a representative sample of a small population requires a relatively larger sample size, which can be both challenging to obtain and costly. In addition to methodological challenges, in many cases, researchers, systems, and surveys simply haven’t asked about sexual orientation and gender identity. While the federal government had been moving towards greater data collection on sexual orientation and gender identity, some of that has been reversed in the second Trump administration and it is still not routine in state and local surveys, or in health systems, providers’ offices and employment, among other settings.

How data are collected is also important for reaching and understanding the needs and experiences of LGBTQ+ people. Best practice suggests data should be collected in ways that align with tested standards, conducted in culturally sensitive ways (accompanied by adequate training), secured responsibly, and then used to improve the lives of the people it represents. (See section on policy impact on LGBTQ+ people’s health.)

Stigma & Discrimination

Copy link to Stigma & Discrimination

Many LGBTQ+ people report having experienced stigma and discrimination in health care and other social institutions due to their actual or perceived sexual orientation, gender identity, and/or gender expression.

KFF polling has shown that LGBT adults face higher rates of discrimination and unfair treatment in their daily lives compared to others, with about two-thirds (65%) saying they have experienced at least one type of discrimination at least a few times in the past year, compared to four in ten non-LGBT adults. (See Figure 2.). These experiences are higher among LGBT adults who are younger and lower income.

Horizontal bar chart compares the share of LGBT adults and non-LGBT adults who report experiencing discrimination or mistreatment in daily life. About 65% of LGBT adults say they experienced at least one type of discrimination at least a few times in the past year, compared with about 40% of non-LGBT adults. The chart includes measures related to discrimination in daily interactions. Across the measures shown, LGBT adults consistently report higher rates of discrimination than non-LGBT adults. These include the following: people act as if they think you are not smart, you are threatened or harassed, you receive poorer service than other people at restaurants or stores, and people act as if they are afraid of you.

The KFF/Washington Post Trans survey found that many trans adults say they feel discriminated against at least “sometimes” due to their gender identity or expression, with trans adults of color even more likely to report multiple types of discrimination, including because of their race or ethnicity, income level or education, or sexual orientation, reflecting how discrimination can cut across intersecting identities. (See Figure 3.)

The figure consists of three groups of stacked bars representing trans adults overall, trans adults of color, and White trans adults. It shows the basis on which trans adults overall, trans adults of color, and White trans adults say they feel discriminated. These bases include gender identity/expression, income/education level, sexual orientation, and race/ethnicity. About two-thirds of trans adults say they experience discrimination related to their gender identity or expression, regardless of their race/ethnicity. The chart shows trans adults of color are more likely to report multiple types of discrimination, including because of their race or ethnicity, income level or education, or sexual orientation.

Experiences of stigma and discrimination also occur in health care settings, in part because pathologizing LGBTQ+ identity, behavior, and desire has a long history in medicine. Indeed, much of the early language of LGBTQ+ identity has its origins in 19th-century psychiatry, which defined LGBTQ+ people in opposition to heterosexual people (and health). The early medical literature promotedthe idea that individuals with LGBTQ+ behavior or desire needed treatment, a notion that persisted for more than a century in dominant medical literature and, in 1952, homosexuality was defined as a psychiatric disorder in the Diagnostic and Statistical Manual of Mental Disorders (DSM), the tool for classifying mental health conditions in the United States; it was not removed as such until 1974 (though as a compromise APA added “sexual orientation disturbance” as diagnosis which was then replaced with “ego dystonic homosexuality” which was not removed until 1987.) While mainstream medicine has evolved from the view of needing to treat LGBTQ+ identity as a medical or psychological disorder, stigma and discrimination within medicine persist.

KFF polling shows that 6 in 10 LGBT adults report at least one of several negative experiences with a health care provider in the past three years – about twice the share of non-LGBT adults who report this. (See Figure 4.)

Horizontal bar chart titled, “LGBT Adults Are Twice as Likely as Non-LGBT Adults to Report Negative Experiences With a Health Care Provider During Recent Visits”,  compares the share of LGBT adults and non-LGBT adults who report experiencing discrimination or unfair treatment from a health care provider. LGBT adults are substantially more likely than non-LGBT adults to report negative experiences in health care settings, including having a provider assume something without asking, being blamed for a health problem, being ignored, or being refused pain medication. 61% of LGBT adults reported at least one of those challenges, compared to 31% non-LGBT adults.

Additionally, about 3 in 10 trans adults say they have had to teach a doctor or other health care provider about trans people to receive appropriate care, had a doctor refuse to acknowledge their preferred gender identity, or been asked unnecessary or invasive questions about their gender identity that were unrelated to their care. (See Figure 5.)

Horizontal bar chart shows the share of trans adults reporting negative experiences in health care settings related to their gender identity. About three in ten trans adults say they had to teach a doctor or other health care provider about trans people in order to receive appropriate care. Similar shares say a provider refused to acknowledge their gender identity and separately asked unnecessary or invasive questions about their gender identity that were unrelated to the reason for their visit. 17% were denied gender affirming care.

Experiences of stigma, discrimination, and mistreatment based on sexual orientation or gender identity occur in multiple non-health care environments and institutions as well, and these also negatively affect health and well-being.

Hate crimes, defined as “bias against people or groups with specific characteristics that are defined by the law,” have negative effects on health, including both physical and psychological harm, and LGBTQ+ people are more likely to experience hate crimes than non-LGTBQ+ people. According to the FBI, in 2023, more than 1 in 5 hate crimes (23%) were related to being LGBTQ+. In 2022, of crimes related to being LGBTQ+, 17% were based on sexual orientation and 4% on gender identity, accounting together for 2,416 crimes in total. Hate crimes against gay men accounted for nearly half (45%) of these, followed by crimes against a combined group of LGBT people (26%), and then transgender people (14%). A smaller share was reported against lesbians (8%), gender non-conforming people (5%), bisexual people (1%), and heterosexual people (1%). (Notably, whether a hate crime gets reported to the FBI and how it is defined are highly variable, so these statistics are likely an underrepresentation of actual crimes that occur.) (See Figure 6.) LGBT+ people are also nine times more likely to self-report that they have experienced a hate crime than non-LGBT+ people.

LGBTQ Related Hate Crimes Reported to the FBI, 2022

Sexual violence, in particular, is a common experience among LGBTQ+ people relative to non-LGBTQ+ people and is especially high among bisexual women and gay and bisexual men. Bisexual women report higher lifetime experiences with rape, other sexual violence and stalking, and lesbian women report higher rates of sexual violence and unwanted sexual contact across their lifetimes than heterosexual women. Gay and bisexual men report higher rates of sexual violence, unwanted sexual experiences, and sexual coercion than heterosexual men, with gay men also reporting higher rates of stalking across their lifetimes than heterosexual men.

Transgender people also face higher rates of intimate partner violence and are more likely to be the victim of a violent crime, with surveys finding that trans people report high rates of violence across a range of measures. KFF polling shows that a majority of trans adults (64%) say they have been verbally attacked and 1 in 4 say they have been physically attacked because of their gender identity, gender expression, or sexual identity. The share of trans adults who have been physically attacked because of their gender identity increases to 31% among trans people of color.

Young LGBTQ+ people are also impacted by higher rates of bullying and violence, including sexual violence, compared to non-LGBTQ+. LGBTQ+ high school students report higher rates of being bullied than non-LGBTQ+ students, with LGBTQ+ students about twice as likely as non-LGBTQ+ students to report that they have been bullied on school property (29% v. 16%) or to report electronic bullying (25% v. 13%). Additionally, LGBTQ+ high school students are twice as likely to report having been injured or threatened with a weapon at school compared to non-LGBTQ+ students (14% v. 7%). Experiences with sexual violence generally (20% v. 8%) and forced sex in particular (17% v. 6%) were also more common among LGBTQ+ high school students than non-LGBTQ+ high school students. (See Figure 7.)

The grouped bar chart compares LGBTQ+ and non-LGBTQ+ high school students experiences related to bullying and violence in 2023. LGBTQ+ students report higher rates than non-LGBTQ+ students across all categories shown: being bullied on school property (29% vs. 16%), electronic bullying (25% vs. 13%), being injured or threatened with a weapon at school (14% vs. 7%), experiencing sexual violence (20% vs. 8%), and experiencing forced sex (17% vs. 6%).

LGBTQ+ people’s disproportionate experiences of maltreatment, stigma, and discrimination can have a significant and negative impact on present and future mental health. Indeed, LGBT adults who had recent experiences with at least one form of discrimination in the past year are more likely to report feeling always or often lonely (42% v. 15%), depressed (38% v. 21%) or anxious (65% v. 34%) than those who rarely or never experienced discrimination in daily life. Additionally, larger shares of LGBT women, younger LGBT adults, and lower-income LGBT adults report regular feelings of anxiety, loneliness, or depression. While other underlying factors beyond discrimination may contribute to these differences, the relationship between feelings of loneliness, anxiety, and depression and experiences with discrimination among LGBT adults remains significant even after controlling for race/ ethnicity, education, income, gender, and age (see section on mental health below). (See Figure 8.)

The grouped bar chart shows differences in experiences of ongoing anxiety, loneliness, and depression among LGBT adults, looking at these experiences among LGBT adults who experienced discrimination in the past year and those who did not. Among those who experienced discrimination, 65% of LGBT adults report feeling anxious always or often anxious, compared with 34% among those who did not. Thirty-eight percent of LGBT adults experiencing discrimination report feeling always or often depressed, compared with 21% among those who did not. Forty-two percent of LGBT adults experiencing discrimination report feeling always or often lonely, compared with 15% among those who did not.

Health Coverage and Access

Copy link to Health Coverage and Access

Overall, LGBT people report similar rates of being uninsured as non-LGBT people (9% v. 10%). LGBT adults, who are notably both younger and lower income than the general population, have higher rates of Medicaid coverage (25% v. 15%) and lower rates of Medicare coverage (8% v. 22%). They are slightly more likely to be covered by private insurance than non-LGBT adults (57% v. 51%). (See Figure 9.)

The grouped bar chart compares health insurance coverage among LGBT adults and non-LGBT adults. Both groups report similar rates of being uninsured (9% for LGBT adults vs. 10% for non-LGBT adults). LGBT adults are more likely to have Medicaid coverage (25% vs. 15%) and slightly more likely to have private insurance (57% vs. 51%). In contrast, LGBT adults are less likely to have Medicare coverage (8% vs. 22%) compared to non-LGB+ adults.

Research has found that having a usual source of care is associated with increased use of preventive care and better health outcomes, but LGBT people are more likely to report not having a usual source of care than non-LGBT people (19% v. 12%). (From KFF’s Survey of Racism, Discrimination, and Health). One study found that LGBTQ people were more likely to lack access to providers, delay care, face issues taking medications due to cost, and have fewer routine checkups than heterosexual cisgender people.

KFF polling has also found that many LGBT adults say negative health care experiences have affected their willingness to seek care, their health care coverage, and their physical health. For example, LGBT adults are significantly more likely than non-LGBT adults to report that having a negative health care experience in the last three years caused their health to get worse (24% v. 9%), made them less likely to seek health care (39% v. 15%), or caused them to switch health care providers (36% v. 16%).

LGBTQ+ People's Health Today

Copy link to LGBTQ+ People's Health Today

While in some areas, the health experiences of LGBTQ+ people mirror those of non-LGBTQ+ people, in other areas, LGBTQ+ people face disparities in health outcomes due to their sexual orientation and gender identity, as well as other factors such as race/ethnicity, class, nationality, and age. Disparities related to mental health, substance use, and sexual health are especially apparent, and LGBTQ+ people also experience certain chronic conditions at higher rates than heterosexual and cisgender people. In some cases, these are driven by social factors such as the biosocial impact of experiencing stigma and discrimination, higher rates of alcohol use and smoking, and obesity. They may also stem from fear of engaging with the health system, including from past experiences of discrimination, which may lead to forgoing routine screening or needed care.

There may also be a link between health care access, competency, and affordability (discussed above) and the ability to detect, control and treat disease. For example, research has found that transgender and gender-diverse people are both less likely to receive cancer screenings and also have a higher incidence of HIV- and HPV-associated cancers.

Overall Health Status

Despite being a younger population, a group traditionally reporting higher levels of well-being, LGBT people are more likely to report being in fair or poor physical health than non-LGBT people (26% v. 19%).

LGBT+ people also report that they are managing chronic conditions and living with disabilities that impact daily life at higher rates than non-LGBT+ people. Half (50%) of LGBT+ people reported that they had an ongoing health condition that requires regular monitoring, medical care, or medication, compared with 45% of non-LGBT+ people. Additionally, one-quarter (25%) of LGBT+ people reported having a disability or chronic disease that keeps them from participating fully in work, school, housework, or other activities, compared with 16% of non-LGBT+ people.

Likewise, a larger share of LGBT+ people report taking at least one prescription medication on a regular basis than non-LGBT+ people (62% v. 55%). This includes more than half (54%) of young LGBT+ adults (ages 18 to 24) who reported regularly taking a prescription compared to just over one-third (36%) of non-LGBT+ adults in the same age group.

Chronic Conditions

Studies have found disparities in certain chronic conditions among LGBTQ+ people, including reports of higher rates of diabetes among lesbians and gay and bisexual men and higher rates of cardiovascular diseases and cancers in certain populations. One study found LGBTQ+ survey respondents were more likely to report having asthma, arthritis, diabetes, kidney disease, hypertension, cardiovascular disease, heart attack, stroke, and chronic obstructive pulmonary disease (COPD) than non LGBTQ+ respondents.

HIV and STIs

There are significant HIV and STI-related disparities among gay and bisexual men, other men who have sex with men, and transgender women compared to other groups and the population as a whole. These disparities may arise for a range of reasons, including sexual networks, differences in behavior, and biological or social factors. In addition, increased incidence of HIV and STIs can, in turn, put these groups at higher risk for other comorbid conditions like other STIs and certain cancers. Nearly three-quarters (71%) of people diagnosed with HIV in 2022 were gay and bisexual men or other men who have sex with men, and of those, young Black and Latino men were disproportionately represented. (See Figure 10.)

Nearly Three-Quarters of HIV Diagnoses in 2022 Were Among Gay and Bisexual Men and Other Men Who Have Sex with Men, Most Were Among Black and Hispanic Men

A meta-analysis estimated that 14% of transgender women and 3% of transgender men are HIV positive. Black and Hispanic transgender women are disproportionately impacted, with prevalence estimates of 44% and 26%, respectively.

Among those seeking care at STD clinics, gay and bisexual men are more likely to test positive for gonorrhea and chlamydia than women or heterosexual men. An estimated 58% of cases of primary and secondary syphilis reported among men with known sex of sex partners in 2023 were among gay and bisexual men and other men who have sex with men, and cases have increased significantly over the past decade. Additionally, the 2022 mpox outbreak occurred almost exclusively among gay and bisexual men and other men who have sex with men, with Black and Hispanic men being especially impacted. While data are limited on gender identity and STIs, studies have indicated that incidence and prevalence levels of gonorrhea and chlamydia among transgender women are similar to those among cisgender gay and bisexual men.

Mental Health and Substance Use

LGBTQ+ people face greater mental health challenges and disparities than non-LGBTQ+ people, including in accessing mental health care. The drivers of these disparities are complex and may relate, in part, to widespread experiences of stigma and discrimination (as described above). Current attempts to institute anti-LGBTQ+ policies in many states and communities may contribute to poor mental health outcomes and increase the need for care.

LGBT adults are more likely than non-LGBT adults to describe their mental health and emotional well-being as either “fair” or “poor” (39% v. 16%). LGBT adults with household incomes below $40,000 are about twice as likely as LGBT adults with higher incomes to report fair or poor mental health (55% v. 27%), as are LGBT adults ages 18-29 compared to those ages 50 and older (56% v. 24%). Across racial and ethnic groups, about 4 in 10 Black (40%), Hispanic (35%) and White (41%) LGBT adults describe their mental health as fair or poor. (See Figure 11.)

The figure shows two columns of bar charts comparing self-reported mental health status between LGBT adults and non-LGBT adults, by different demographic variables. OverallOverall, it show 39% of LGBT adults describe their mental health as fair or poor, compared with 16% of non-LGBT adults. LGBT adults who are younger or lower income are most likely to report poor or fair mental health.  Differences are smaller by gender and similar across race/ethnicities.

More specifically, about half (54%) of LGBT adults report feeling anxious either “always” or “often” in the past year, while a third report feeling lonely (33%) or depressed (32%) “always” or “often” – more than twice the shares of non-LGBT adults who report the same. As noted earlier, those who experienced recent discrimination were more likely to report these feelings than those who did not. 

LGB adults also report having serious thoughts of suicide, making a suicide plan, or attempting suicide at higher rates than non-LGB adults, with disparities especially pronounced among bisexual adults. LGB adults also report higher rates of substance use and substance use disorder (SUD) than non-LGB adults, with rates especially high among bisexual adults.

KFF’s polling of trans adults shows that many struggle with serious mental health issues, including 4 in 10 (43%) who say they have had suicidal thoughts in the past year. Trans adults are about six times as likely as cisgender adults to say they have engaged in self-harm in the past year, and more than twice as likely to say they have had an eating disorder in the past year or had suicidal thoughts in the past year. (See Figure 12.)

The figure consists of three groups of stacked bars representing trans adults, LGBT adults, and cisgender adults. It shows the share of each group that has experienced specific mental health challenges including the following in the past 12 months: suicidal thoughts, an eating disorder, misused drugs or alcohol, engaged in self-harm. The chart shows many trans adults struggle with serious mental health issues, at times at higher rates than LGBT people overall, and consistently more commonly than cisgender adults. This includes 43% of trans adults who say they have had suicidal thoughts in the past year compared to 34% of LGBT adults and 16% of cisgender adults and 17% who engaged in self-harm compared to 10% of LGBT adults and 3% of cisgender adults.

Mental health disparities are especially significant among young LGBTQ+ people. In 2023, more than half (53%) of LGBTQ+ high school students reported poor mental health in the past 30 days compared to 1 in 5 (21%) non-LGBTQ+ students and more than twice as many reported persistent feelings of sadness or hopelessness over the past year (65% among LGBTQ+ students compared to 31% among non-LGBTQ+ students). In addition, 41% of LGBTQ+ high school students reported having seriously considered suicide during the past year, with 20% having attempted suicide, rates that are substantially higher than for non-LGBTQ+ students (13% and 6%, respectively). (See Figure 13.)

A bar chart compares LGBTQ+ and non-LGBTQ+ high school students across several mental health measures. LGBTQ+ students report substantially higher rates of poor mental health in the past 30 days (53% vs. 21%), persistent feelings of sadness or hopelessness during the past year (65% vs. 31%), seriously considering suicide during the past year (41% vs. 13%), and attempting suicide during the past year (20% vs. 6%).

Substance use rates were also higher among LGBTQ+ high school students than their non-LGBTQ+ peers.LGBTQ+ students and students with any same-sex partners were more likely to engage in a range of substance use behaviors than their peers, including use of alcohol, marijuana, any illicit drug, vaping, and prescription opioids.

In addition to higher reported rates of mental health challenges, LGBT people, particularly those in fair or poor mental health and younger adults, report greater challenges accessing mental health care and are more likely to report forgoing needed mental health care than non-LGBT adults. About half (46%) of LGBT adults say there was a time in the past three years when they thought they might need mental health services but didn’t get them, more than twice the share of non-LGBT adults who say so (20%). Reported challenges to care include affordability and accessibility of providers, including finding a provider who can relate to their background and experiences.

Best Practices for Competent Care

Copy link to Best Practices for Competent Care

Access to competent and inclusive health care that meets the needs of LGBTQ+ people can improve engagement with the health system and, ultimately, health outcomes.

The American Medical Association (AMA) provides recommended standards of practice with LGBTQ patients and resources to help make medical practices LGBTQ-friendly, such as including posters, brochures, and other materials that are LGBTQ-inclusive, revising intake materials to be affirming and inclusive, and participating in further provider education.

Similarly, the American Psychiatric Association also provides guidance, including acknowledgment of the role the association played in perpetuating stigma for LGBTQ+ people in the past and guiding practitioners to not make assumptions about sexual orientation or gender identity in gathering medical information, reminding providers that families can be helped to move towards more acceptance of LGBTQ+ children to improve their mental health, and explicitly coming out against ‘conversion or reparative’ therapy. Indeed, the use of “conversion therapy” is condemned among all major health groups, 28 of which signed a 2023 joint statement against its use, stating that such interventions are both ineffective and harmful, and about half of states have enacted a ban on coverage therapy for minors.

Other resources highlight the importance of language use in caring for LGBTQ+ people, including when it comes to how sexual orientation and gender are discussed and described and how patients are addressed with respect to names and pronoun use. Leadership “buy-in” and the role of LGBTQ+ champions are also highlighted, as are the benefits of inclusive policies. Data collection used to improve health outcomes, staff training, and partnering locally with the LGBTQ+ community are also noted as ways to be a more affirming practice.

Providing health care services or competent referrals for health services that are disproportionately needed by the LGBTQ+ community is another way to offer inclusive care. This might include behavioral health services, STI care and screening, or inclusive family planning services. Another such service is gender affirming care (see below).

Gender Affirming Care

Copy link to Gender Affirming Care

Gender affirming care is a model of care which includes a spectrum of “medical, surgical, mental health, and non-medical services for transgender and nonbinary people” aimed at affirming and supporting an individual’s gender identity.Gender affirmation is highly individualized. Not all trans people seek the same types of gender affirming care or services and some people choose not to use medical services as a part of their transition. Gender affirming care is tailored to an individual’s needs across the lifespan.

Virtually all major U.S. medical associations support youth access to gender affirming care, including the American Medical Association, American Academy of Pediatrics, and the American Psychological Association, among others. In particular, these groups point to the evidence demonstrating that medically necessary gender affirming care enhances mental health outcomes for transgender youth, including by reducing suicidal ideation. Professional guidance for gender affirming care, including for young people, is provided by the Endocrine Society and the World Professional Association for Transgender Health, bodies that also support access to this care model.

There is no one way to transition. KFF polling finds commonly utilized gender affirming activities are related to a social transition, such as changing the types of clothes worn (77%), changing hairstyles/grooming habits (76%), or going by different pronouns (72%). Slightly fewer, but still a majority, of trans adults use a different name than the one on their birth certificate (57%). Fewer than half of trans adults report attending counseling or therapy as a part of their gender transition (38%) (which is sometimes a requirement for other gender affirming care), legally changing their name on identifying documents (24%), or using hormone treatments or puberty-blocking hormones (31%) Despite common rhetoric, surgical care is a rare component of gender affirming care, with just 16% of trans adults reporting having received gender-affirming surgery. While the number of young trans people using puberty blockers or hormone therapy has increased modestly in recent years, the overall number of those using these prescriptions remains fairly low and multiple studies have shown gender affirming surgery is extremely rare among minors.

Lack of insurance coverage for gender affirming care is a barrier to receiving these services. KFF’s polling finds, for example, that among trans adults with health insurance, about a quarter (27%) say their insurance covers gender affirming treatment or health care, while 14% say their health insurance does not cover this and 6 in 10 (58%) are unsure. One in 5 trans adults say they have had health insurance that would not cover gender affirming treatments or health care (22%). About 1 in 7 trans adults have changed jobs or health insurance in order to get gender affirming treatments or health care. (See Figure 14.)

This bar chart, titled “One in Five Trans Adults Say They Have Had Health Insurance That Would Not Cover Gender Affirming Treatments or Gender Affirming Care” presents experiences related to insurance coverage for gender-affirming care among trans adults. 22% of trans adults say their insurance would not cover gender-affirming health care, 15% say they have changed jobs or to get insurance covering care, 14% say they changed health insurance providers to get coverage, and 14% say they have gone on someone else’s insurance to get coverage.

Despite the evidence around the role gender affirming care can play in promoting well-being for young people and support from the medical community, some have argued against this care claiming that the services are experimental and lack an evidence base or that young trans people commonly change their minds about their gender identity. The Trump administration, in particular, has moved to limit access to gender affirming care, particularly for youth, through executive orders and other actions (see discussion below). The administration has also promoted misinformation about gender affirming care relating to issues like regret rates, how common surgical care is, and conflating it with female genital mutilation. It has stated that it will seek to prohibit providers receiving federal funding from providing certain gender affirming care services to minors. To date, more than half (27) of US states (as of July 2025) have enacted restrictions on gender affirming care for minors (discussed further below). As a result, young people may be unable to get medically necessary care depending on where they live and the resources their families have. Research has demonstrated that young transgender people’s mental health is negatively impacted when this care is denied, including leading to an increased risk of suicidality. Further, claims around lack of evidence and regret are not borne out by the data and, in fact, the very same services are provided to young people in other medical circumstances without controversy. 

Policy Impact

Copy link to Policy Impact

Policymaking, including in health care, can both facilitate and hinder access to care and coverage, and ultimately, health outcomes, for LGBTQ+ people. Recent examples of how policymaking addresses LGBTQ+ people’s health include:

Supreme Court of the United States (SCOTUS) Decisions: Several recent Supreme Court decisions have impacted the health and well-being of LGBTQ+ people. SCOTUS decisions regarding marriage equality have been particularly far reaching with both the Windsor (2013) and Obergefell (2015) decisions providing same-sex married couples with legal access to spousal health insurance benefits for the first time, among other changes. In Bostock (2019), SCOTUS ruled that in the context of employment, discrimination based on sex encompasses sexual orientation and gender identity—a decision that was subsequently used to support extending sex protections in health care to LGBTQ+ people (see discussion of Section 1557 below). In June 2025, in United States v. Skrmetti, SCOTUS ruled that a Tennessee law banning gender affirming care for minors did not violate the 14th Amendment’s Equal Protection clause, allowing it and other similar laws to remain in place, resulting in a continued patchwork of access. On March 10, 2025, SCOTUS granted certiorari in Chiles v. Salazar and will review a challenge to Colorado's conversion therapy ban for minors, assessing “whether a law that censors certain conversations between counselors and their clients based on the viewpoints expressed regulates conduct or violates the Free Speech Clause.” 

  • Section 1557: One area that has received significant attention over the last decade is Section 1557 of the Affordable Care Act (ACA). Section 1557 prohibits discrimination on the basis of a range of factors, including sex, and applies to health programs and activities receiving federal financial assistance (referred to as covered entities). Specifically, it prevents covered entities from discriminating against certain protected groups in providing health care services, insurance coverage, and program participation. Across different Presidential administrations, lengthy rulemaking and court challenges have affected the application of Section 1557, particularly around whether sexual orientation and gender identity should be encompassed in sex protections. The Obama administration interpreted the statute to include protections on the basis of gender identity and sex-stereotyping, laying out specific protections for trans people, while the Trump administration removed such protections. The Biden administration has since restored and expanded on protections, including by also interpreting sex protections to protect against discrimination on the basis of sexual orientation, following the Bostock decision. As of May 2025, the Trump administration had not yet issued rulemaking on Section 1557, but multiple executive orders suggest that the administration will view sex narrowly, laying the groundwork for removing explicit protections for LGBTQ+ people.
  • Mental Health: Policy can also positively or negatively impact the mental health of the LGBTQ+ community. For example, 988, the federally-mandated suicide and crisis line, supported by the Substance Abuse and Mental Health Services Administration (SAMHSA), historically included specific services to meet the needs of LGBTQ+ young people. While the service represented 10% of all contacts to 988 funded by Congress, the Trump administration ended this service in July 2025. Under the Biden administration, SAMHSA released a “road map” for supporting LGBTQ+ youth, an LGBTQI+ Family Support Grant providing nearly $2 million in funding for programs that address behavioral health for LGBTQ youth, and more than $5 million for “Family Counseling and Support for Lesbian, Gay, Bisexual, Transgender, Queer/Questioning, Intersex+ Youth and their Families,” and also funded the Center of Excellence: LGBTQ+ Behavioral Health Equity aimed at supporting “implementation of change strategies within mental health and substance use disorder treatment systems to address disparities impacting the LGBTQ+ community.” The Biden administration issued a rule to better protect LGBTQ+ youth in foster care. In addition to federal efforts, some states are also electing to highlight and address the behavioral health needs of LGBTQ+ people, sometimes through the use of federal funds. On the other hand, there is evidence that the promulgation of state laws and policies restricting access to LGBTQ+ health and other services negatively affects the mental health of the community. The Trump administration’s approach to LGBTQ people’s health has differed significantly. Following President Trump’s campaign promises, the administration has prioritized actions and policymaking aimed at limiting young people’s access to gender affirming care and, in some cases, denying existence of transgender people and fueling misinformation about transgender and intersex people and trans health care. The administration has reversed Biden-era agendas, roadmaps, and interpretations of civil rights protections regarding LGBTQ people’s well-being. Collectively, these actions can have a negative impact on well-being and access to medically necessary best practice care.
  • Gender affirming care: As noted above, the Trump administration has taken a range of actions and made proposals to limit gender affirming care for minors, differing from the Biden administration which had supported access to this care on principles of equity and well-being. These orders have generally sought to restrict access to services, limit research related to gender diversity, and stated that the federal government will only acknowledge two sexes and will not recognize diverse gender identities, including transgender people. As of July 2025, most of these actions do not formally prohibit entities from providing care, but they have led to a climate of fear and a chilling effect, with many providers walking back gender affirming care services for minors. Actions that led to this include creating an FBI tip line to report clinicians providing surgical care to minors, detailed collection of personal and institutional information offering gender affirming care, issuing subpoenas, and explicitly stating that the administration is seeking to make providing gender affirming care to minors a violation of terms of condition for participation in the Medicare and Medicaid programs, among others. Further actions limiting access are expected, as is litigation challenging these restrictions. The administration also released an evidence review related to information about treatment of gender dysphoria, concluding that the quality of evidence on the effects of intervention is low, and evidence on harms is “sparse.” It also states that there are significant risks and supports the use of psychotherapeutic approaches, including an approach termed “exploratory therapy”, which can include conversion therapy, departing from most U.S. medical associations. While the report has been used to promote restrictions, it has also faced criticism including for its approach to the review and promotion of misinformation, among other factors. Impacting both adults and minors, the administration also adopted a policy that would not require broad financial protections in the individual market and small group health insurance marketplaces from applying to gender affirming care.
  • Data collection: (See also callout box on data collection.)Better understanding who the LGBTQ+ community is and what challenges they face allows policymakers, providers, and other individuals and groups to meet their needs better and provide care and coverage that is culturally competent. Addressing care needs may happen in the provider’s office, at the health system level, or in the policy arena. Research on LGBTQ+ people and health has generally increased over time though that trend is currently reversing at the federal level. Both the Obama and Biden administrations implemented a range of efforts to improve collection and reporting of data on LGBTQ+ people. For example, in 2016, the NIH designated sexual and gender minorities (SGMs) as a health disparity population for research purposes. In doing so, NIH recognized the health disparities faced by this population and that “the extent and causes of health disparities are not fully understood, and research on how to close these gaps is lacking.” Many federal surveys also began to ask sexual orientation and gender identity (SOGI) questions, including the Behavioral Risk Factor Surveillance System Survey, the National Survey on Drug Use, the National Health Interview Survey, and the Youth Risk Behavior Survey, though data collection was not routine and it was sometimes an optional variable for states or a restricted variable for researchers. The Biden administration also issued an executive order calling for agencies to enhance routine collection of SOGI data to improve outcomes and address disparities, and an implementing roadmap in a Federal Evidence Agenda. However, SOGI data collection has become politicized. The first Trump administration sought to roll back some of the activities of the Obama administration, and these efforts have intensified in President Trump’s second term. On his first day in office President Trump rescinded the Biden-era executive order on data collection and issued executive orders taking a narrow view of sex and removing recognition of gender identity and limiting diversity, equity, inclusion, and accessibility (DEIA) activities in government programs, which led to limiting data collection efforts. A range of datasets, questionnaires, codebooks, reports, and other documents were removed from federal websites in the early days of the administration (some of which have been reposted due to a court order)and SOGI data collection in major surveys, including the Census, have been discontinued to comply with executive orders. Beyond survey data, data collection is also limited by efforts to rescind LGBTQ related research funding. Data collection efforts are also variable at state and health system levels and, if not reliant on federal funding, may be able to continue.
  • State and Local Policymaking: While federal policymaking plays an important role in individuals’ lives, so too does state and local policymaking, perhaps, especially so in health care. Over the past few years, there has been a rash of policymaking addressing LGBTQ+ people’s health. Policies have both aimed to expand protections and well-being for LGBTQ+ people and sought to restrict access to care or loosen antidiscrimination standards. For example, as of July 2025, over half of states have enacted policies aimed at limiting or prohibiting youth access to gender affirming care and most of this policymaking took place within an 18-month period . Other states have enacted “refuge laws” (also known as “shield laws”) that generally aim to protect individuals, families, and providers living in states where these bans have been enacted. State policymaking has also focused on LGBTQ+ people and access to services through private and public insurance coverage. For example, while some states expressly prohibit insurers from discriminating against people based on sexual orientation and gender identity, others are silent on the issue. Similarly, some state Medicaid programs explicitly cover gender affirming care, others have exclusions, and some have no clear policy; even those that do cover this care may not cover all the services an individual needs. About half of states have enacted laws banning conversion therapy for minors, but the Supreme Court is set to hear a challenge to Colorado’s ban in the fall of 2025. Finally, some LGBTQ+ related policy is not overtly health-related but has the potential to impact well-being. For example, preventing schools from adopting LGBTQ+ anti-bullying policies or enacting laws that require school staff to out transgender youth to their families stand to negatively impact health outcomes.

Future Outlook

Copy link to Future Outlook

Despite the increase in the share of people identifying as LGBTQ+ and in public support for LGBTQ+ relationships and protections against discrimination, LGBTQ+ people continue to face health disparities and worse health outcomes in several areas. In many cases, these are directly related to ongoing experiences of stigma, discrimination, and violence. Policy efforts to address health disparities among LGBTQ+ people, including those tied to experiences of stigma and discrimination, had increased over time but under the second Trump administration are reversing, with numerous executive branch actions designed to limit access to care and remove protections for LGBTQ+ people.  More generally, there has been growing partisanship in some areas of LGBTQ+ rights and access, particularly for LGBTQ+ youth, and a rise in the number of policies and laws that restrict access to recommended care. Monitoring these policies, the shifting legal landscape, and better understanding the actual experiences of LGBTQ+ people will help inform efforts to address and mitigate health disparities for this population moving forward.

Resources

Copy link to Resources

Citation

Copy link to Citation

Dawson, L., Kates, J., Montero, A., and Kirzinger, A., LGBTQ+ Health Policy. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-lgbtq-health-policy/ (date accessed).

Congress and the Executive Branch and Health Policy

KFF Author:

Table of Contents

Introduction

Copy link to Introduction

The federal government is not the only place health policy is made in the U.S., but it is by far the most influential. Of the $4.9 trillion the U.S. spent on health in 2023, the federal government was responsible for roughly a third of all health services. The payment and coverage policies set for the Medicare program, in particular, often serve as a model for the private sector. Many health programs at the state and local levels are also impacted by federal health policy, either through direct spending or rules and requirements. Federal health policy is primarily guided by Congress, but carried out by the executive branch, predominantly by the Department of Health and Human Services. 

The Federal Role in Health Policy 

Copy link to The Federal Role in Health Policy 

No one is “in charge” of the fragmented U.S. health system, but the federal government probably has the most influence, a role that has grown over the last 75 years. Today the federal government pays for care, provides it, regulates it, and sponsors biomedical research and medical training.  

The federal government pays for health coverage for well over 100 million Americans through Medicare, Medicaid, the Children’s Health Insurance Program (CHIP), the Veterans’ Health Administration, the Indian Health Service, and the Affordable Care Act (ACA).  It also pays to help provide insurance coverage for tens of millions who are active-duty and retired military and for civilian federal workers.

Federal taxpayers also underwrite billions of dollars in health research, mainly through the National Institutes of Health (NIH) and the Agency for Healthcare Research and Quality (AHRQ).

Federal public health policy is spearheaded by the Centers for Disease Control and Prevention. Its portfolio includes tracking not just infectious disease outbreaks in the U.S. and worldwide, but also conducting and sponsoring public health research and tracking national health statistics. 

The Health Resources and Services Administration (HRSA) funds critical health programs for underserved Americans (including Community Health Centers) and runs workforce education programs to bring more health services to places without enough health care providers. 

Meanwhile, in addition to overseeing the nation’s largest health programs, the Centers for Medicare and Medicaid Services (CMS) also operates the federal insurance Marketplaces created by the ACA and enforces rules made by the law for private insurance policies. 

While the federal government exercises significant authority over medical care and its practice and distribution, state and local governments still have key roles to play.  

States oversee the licensing of health care professionals, distribution of health care resources, and regulation of health insurance plans that are not underwritten by employers themselves. State and local governments share responsibility for most public health activities and often operate safety-net facilities in areas with shortages of medical resources. 

The Three Branches of Government and How They Impact Health Policy 

Copy link to The Three Branches of Government and How They Impact Health Policy 

All three branches of the federal government – Congress, the executive branch, and the judiciary – play important roles in health policy. 

Congress makes laws that create new programs or modify existing ones. It also conducts “oversight” of how the executive branch implements the laws Congress has passed. Congress also sets the budget for “discretionary” and “mandatory” health programs (see below) and provides those dollar amounts. 

The executive branch carries out the laws made by Congress and operates the federal health programs, often filling in details Congress has left out through rules and regulations. Federal workers in the health arena may provide direct patient care, regulate how others provide care, set payment rates and policies, conduct medical or health systems research, regulate products sold by the private sector, and manage the billions of dollars the federal government spends on the health-industrial complex.  

Historically, the judiciary has had the smallest role in health policy, but has played a pivotal role in recent cases. It passes judgment on how or whether certain laws or policies can be carried out and settles disputes between the federal government, individuals, states, and private companies over how health care is regulated and delivered.  Recent significant decisions from the Supreme Court have affected the legality and availability of abortion and other reproductive health services and the constitutionality of major portions of the ACA.

The Executive Branch – The White House

Although most of the executive branch’s health policies are implemented by the Department of Health and Human Services (and to a smaller extent, the Departments of Labor and Justice), over the past several decades the White House itself has taken on a more prominent role in policy formation. The White House Office of Management and Budget not only coordinates the annual funding requests for the entire executive branch, but it also reviews and approves proposed regulations, Congressional testimony, and policy recommendations from the various departments. The White House also has its own policy support agencies – including the National Security Council, the National Economic Council, the Domestic Policy Council, and the Council of Economic Advisors – that augment what the President receives from other portions of the executive branch.

How the Department of Health and Human Services is Structured

Copy link to How the Department of Health and Human Services is Structured

Most federal health policy is made through the Department of Health and Human Services. Exceptions include the Veterans Health Administration, run by the Department of Veterans Affairs; TRICARE, the health insurance program for active-duty military members and dependents, run by the Defense Department; and the Federal Employees Health Benefits Program (FEHB), which provides health insurance for civilian federal workers and families and is run by the independent agency the Office of Personnel Management.  

The health-related agencies within HHS are roughly divided into the resource delivery, research, regulatory, and training agencies that comprise the U.S. Public Health Service and the health insurance programs run by the Centers for Medicare and Medicaid Services (CMS). 

Ten of the 13 operating divisions of HHS are part of the U.S. Public Health Service, which also plays a role in U.S. global health programs. They are: 

  • The Administration for Strategic Preparedness and Response (ASPR) 
  • The Advanced Research Projects Agency for Health (ARPA-H)
    • The Agency for Healthcare Research and Quality (AHRQ) 
    • The Agency for Toxic Substances and Disease Registry (ATSDR) 
    • The Centers for Disease Control and Prevention (CDC) 
    • The Food and Drug Administration (FDA) 
    • The Health Resources and Services Administration (HRSA) 
    • The Indian Health Service (IHS) 
    • The National Institutes of Health (NIH) 
    • The Substance Abuse and Mental Health Services Administration (SAMHSA) 

The Centers for Medicare and Medicaid Services (CMS) is by far the largest operating division of HHS. It oversees not just the Medicare and Medicaid programs, but also the federal Children’s Health Insurance Program (CHIP) and the health insurance portions of the Affordable Care Act. Together, the programs under the auspices of CMS account for nearly a quarter of all federal spending in fiscal 2023, cost an estimated $1.5 trillion in fiscal 2023, and served more than 170 million Americans – more than half the population.

The current Trump administration has proposed a major restructuring of the health agencies under HHS, including creation of a new “Administration for a Healthy America.” As of September 2025, that restructuring has been blocked by court action.  However, a data analysis conducted by the news organization ProPublica found that as of August 2025, more than 20,500 workers – about 18 percent of the department’s workforce – had been laid off or left their jobs.

Who Makes Health Policy in Congress?

Copy link to Who Makes Health Policy in Congress?

How Congress oversees the federal health care-industrial complex is almost as byzantine as the U.S. health system itself. Jurisdiction and responsibility for various health agencies and policies is divided among more than two dozen committees in the House and Senate (Tables 1 and 2). 

In each chamber, however, three major committees deal with most health issues.  

In the House, the Ways and Means Committee, which sets tax policy, oversees Part A of Medicare (because it is funded by the Social Security payroll tax) and shares jurisdiction over other parts of the Medicare program with the Energy and Commerce Committee. Ways and Means also oversees tax subsidies and credits for the Affordable Care Act and tax policy for most employer-provided insurance.  

The Energy and Commerce Committee has sole jurisdiction over the Medicaid program in the House and shares jurisdiction over Medicare Parts B, C, and D with Ways and Means. Energy and Commerce also oversees the U.S. Public Health Service, whose agencies include the Food and Drug Administration, the National Institutes of Health, and the Centers for Disease Control and Prevention.  

While Ways and Means and Energy and Commerce are in charge of the policymaking for most of the federal government’s health programs, the actual amounts allocated for many of those programs are determined by the House Appropriations Committee through the annual Labor-Health and Human Services-Education and Related Agencies spending bill.  

In the Senate, responsibility for health programs is divided somewhat differently. The Senate Finance Committee, which, like House Ways and Means, is in charge of tax policy, oversees all of Medicare and Medicaid and most of the ACA.  

The Senate counterpart to the House Energy and Commerce Committee is the Senate Health, Education, Labor and Pensions Committee, which has jurisdiction over the Public Health Service (but not Medicare or Medicaid).  

The Senate Appropriations Committee, like the one in the House, sets actual spending for discretionary programs as part of its annual Labor-HHS-Education spending bill. 

Senate Committees with Health Jurisdiction
House Committees with Health Jurisdiction

The Federal Budget Process

Copy link to The Federal Budget Process

Under Article 1 of the U.S. Constitution, Congress is granted the exclusive power to “lay and collect Taxes, Duties, Imposts and Excises, and to pay the Debts and provide for the common Defence and General Welfare of the United States.”  

In 1974, lawmakers passed the Congressional Budget and Impoundment Control Act in an effort to standardize the annual process for deciding tax and spending policy for each federal fiscal year and to prevent the executive branch from making spending policy reserved to Congress. Among other things, it created the House and Senate Budget Committees and set timetables for each step of the budget process.  

Perhaps most significantly, the 1974 Budget Act also created the Congressional Budget Office (CBO). This non-partisan agency has come to play a pivotal role in not just the budget process, but in the lawmaking process in general. The CBO issues economic forecasts, policy options, and other analytical reports, but it most significantly produces estimates of how much individual legislation would cost or save the federal government. Those estimates can and do often determine if legislation passes or fails.

The annual budget process is supposed to begin the first Monday in February, when the President is to present his proposed budget for the fiscal year that begins the following Oct. 1. This is one of the few deadlines in the Budget Act that is usually met. 

After that, the action moves to Congress. The House and Senate Budget Committees each write their own “Budget Resolution,” a spending blueprint for the year that includes annual totals for mandatory and discretionary spending. Because mandatory spending (roughly two-thirds of the budget) is automatic unless changed by Congress, the budget resolution may also include “reconciliation instructions” to the committees that oversee those programs (also known as “authorizing” committees) to make changes to bring the cost of the mandatory programs in line with the terms of the budget resolution. The discretionary total will eventually be divided by the House and Senate Appropriations Committees between the 12 subcommittees, each responsible for a single annual spending (appropriations) bill. Most of those bills cover multiple agencies – the appropriations bill for the Department of Health and Human Services, for example, also includes funding for the Departments of Labor and Education.  

After the budget resolution is approved by each chamber’s Budget Committee, it goes to the House and Senate floor, respectively, for debate. Assuming the resolutions are approved, a “conference committee” comprised of members from each chamber is tasked with working out the differences between the respective versions. A final compromise budget resolution is supposed to be approved by both chambers by April 15 of each year. (This rarely happens.) Because the final product is a resolution rather than a bill, the budget does not go to the President to sign or veto.  

The annual appropriations process kicks off May 15, when the House may start considering the 12 annual spending bills for the fiscal year that begins Oct. 1. By tradition, spending bills originate in the House, although sometimes, if the House is delayed in acting, the Senate will take up its own version of an appropriation first. The House is supposed to complete action on all 12 spending bills by June 30, in order to provide enough time to let the Senate act, and for a conference committee to negotiate a final version that each chamber can approve by October 1. 

That October 1 deadline is the only one with consequences if it is not met. Unless an appropriations bill for each federal agency is passed by Congress and signed by the President by the start of the fiscal year, that agency must shut down all “non-essential” activities funded by discretionary spending until funding is approved. Because Congress rarely passes all 12 of the appropriations bills by the start of the fiscal year (the last time was in 1996, for fiscal year 1997), it can buy extra time by passing a “continuing resolution” (CR) that keeps money flowing, usually at the previous fiscal year’s level. CRs can last as little as a day and as much as the full fiscal year and may cover all of the federal government (if none of the regular appropriations are done) or just the departments for the unfinished bills. Congress may, and frequently does, pass multiple CRs while it works to complete the appropriations process. 

While each appropriations bill is supposed to be considered individually, to save time (and sometimes to win needed votes), a few, several, or all the bills may be packaged into a single “omnibus” measure. Bills that package only a handful of appropriations bills are cheekily known as “minibuses.”  

Meanwhile, if the budget resolution includes reconciliation instructions, that process proceeds on a separate track. The committees in charge of the programs requiring alterations each vote on and report their proposals to the respective budget committees, which assemble all of the changes into a single bill. At this point, the budget committees’ role is purely ministerial; it may not change any of the provisions approved by the authorizing committees.  

Reconciliation legislation is frequently the vehicle for significant health policy changes, partly because Medicare and Medicaid are mandatory programs. Reconciliation bills are subject to special rules, notably on the Senate floor, which include debate time limitations (no filibusters) and restrictions on amendments. Reconciliation bills also may not contain provisions that do not pertain directly to taxing or spending. 

Unlike the appropriations bills, nothing happens if Congress does not meet the Budget Act’s deadline to finish the reconciliation process, June 15. In fact, in more than a few cases, Congress has not completed work on reconciliation bills until the calendar year AFTER they were begun.   

A (Very Brief) Explanation of the Regulatory Process

Copy link to A (Very Brief) Explanation of the Regulatory Process

Congress writes the nation’s laws, but it cannot account for every detail in legislation. So, it often leaves key decisions about how to interpret and enforce those laws to the various executive departments. Those departments write (and often rewrite) rules and regulations according to a very stringent process laid out by the 1946 Administrative Procedure Act (APA). The APA is intended to keep the executive branch’s decision-making transparent and to allow public input into how laws are interpreted and enforced.

Most federal regulations use the APA’s “informal rulemaking” process, also known as “notice and comment rulemaking,” which consists of four main parts: 

  • Publication of a “Notice of Proposed Rulemaking (NPRM)” in the Federal Register, a daily publication of executive branch activities. 
  • Solicitation to the public to submit written comments for a specific period of time (usually from 30 to 90 days). 
  • Agency consideration of public reaction to the proposed rule; and, finally 
  • Publication of a final rule, with an explanation including how the agency took the public comments into account and what changes, if any, were made from the proposed rule. Final rules also include an effective date, which can be no less than 30 days but may be more than a year in the future. 

In situations where time is of the essence, federal agencies may truncate that process by issuing “interim final rules,” which can take effect even before the public is given a chance to comment. Such rules may or may not be revised later.  

Not all federal interpretation of laws uses the APA’s specified regulatory process. Federal officials also distribute guidance, agency opinions, or “statements of policy.” 

Future Outlook

Copy link to Future Outlook

Given how fragmented health policy is in both Congress and the executive branch, it should not be a surprise that major changes are difficult and rare.  

Add to that an electorate divided over whether the federal government should be more involved or less involved in the health sector, and huge lobbying clout from various interest groups whose members make a lot of money from the current operation of the system, and you have a prescription for inertia. 

Sometimes change does happen suddenly, however. In 2025, Republicans in control of the House, Senate, and White House narrowly passed a budget reconciliation bill that is projected to make deep cuts to the Medicaid program as well as add new barriers for people to maintain or enroll in health insurance under the ACA.

Another potential wildcard—in June of 2024, the Supreme Court overturned a 40-year-old precedent, known as “Chevron deference,” that gave the benefit of the doubt in interpreting ambiguous laws passed by Congress to federal agencies rather than judges. Overturning Chevron will likely make it easier for outsiders to challenge federal agency actions, but it will be some time before the full ramifications become clear.   

Another problem is that when a new health policy can dodge the minefield of obstacles to become law, it almost by definition represents a compromise that may help it win enough votes for passage, but is more likely to complicate an already byzantine system further. 

Unless the health system completely breaks down, it seems unlikely that federal policymakers will be able to move the needle very far in either a conservative or a liberal direction, although the second Trump administration is attempting to circumvent Congress entirely to remake federal health agencies and how they work. Whether that will withstand review by the courts remains to be seen.

Resources

Copy link to Resources

Citation

Copy link to Citation

Rovner, J., Congress, the Executive Branch, and Health Policy. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-congress-and-the-executive-branch-and-health-policy/ (date accessed).

The Politics of Health Care and Elections

Table of Contents

Introduction

Copy link to Introduction

Health policy and politics are inextricably linked. Policy is about what the government can do to shift the financing, delivery, and quality of health care, so who controls the government has the power to shape those policies.

Elections, therefore, always have consequences for the direction of health policy – who is the president and in control of the executive branch, which party has the majority in the House and the Senate with the ability to steer legislation, and who has control in state houses. When political power in Washington is divided, legislating on health care often comes to a standstill, though the president still has significant discretion over health policy through administrative actions. And, stalemates at the federal level often spur greater action by states.

Health care issues often, but not always, play a dominant role in political campaigns. Health care is a personal issue, so it often resonates with voters. The affordability of health care, in particular, is typically a top concern for voters, along with other pocketbook issues, and, at over 17% of the economy, health care has many industry stakeholders who seek influence through lobbying and campaign contributions. At the same time, individual policy issues are rarely decisive in elections.

Health Reform in Elections

Copy link to Health Reform in Elections

Health “reform” – a somewhat squishy term generally understood to mean proposals that significantly transform the financing, coverage, and delivery of health care – has a long history of playing a major role in elections.

Harry Truman campaigned on universal health insurance in 1948, but his plan went nowhere in the face of opposition from the American Medical Association and other groups. While falling short of universal coverage, the creation of Medicare and Medicaid in 1965 under Lyndon Johnson dramatically reduced the number of uninsured people. President Johnson signed the Medicare and Medicaid legislation at the Truman Library in Missouri, with Truman himself looking on.

Later, Bill Clinton campaigned on health reform in 1992, and proposed the sweeping Health Security Act in the first year of his presidency. That plan went down to defeat in Congress amidst opposition from nearly all segments of the health care industry, and the controversy over it has been cited by many as a factor in Democrats losing control of both the House and the Senate in the 1994 midterm elections.

For many years after the defeat of the Clinton health plan, Democrats were hesitant to push major health reforms. Then, in the 2008 campaign, Barack Obama campaigned once again on health reform, and proposed a plan that eventually became the Affordable Care Act (ACA). The ACA ultimately passed Congress in 2010 with only Democratic votes, after many twists and turns in the legislative process. The major provisions of the ACA were not slated to take effect until 2014, and opposition quickly galvanized against the requirement to have insurance or pay a tax penalty (the “individual mandate”) and in response to criticism that the legislation contained so-called “death panels” (which it did not). Republicans took control of the House and gained a substantial number of seats in the Senate during the 2010 midterm elections, fueled partly by opposition to the ACA.

The Affordable Care Act (Obamacare)

Copy link to The Affordable Care Act (Obamacare)

The ACA took full effect in 2014, with millions gaining coverage, but more people viewed the law unfavorably than favorably, and repeal became a Republican rallying cry in the 2016 campaign. After the election of Donald Trump, a high-profile effort to repeal the law was ultimately defeated following a public backlash. The ACA repeal debate was a good example of the trade-offs inherent in all health policies. Republicans sought to reduce federal spending and regulation, but the result would have been fewer people covered and weakened protections for people with pre-existing conditions. KFF polling showed that the ACA repeal effort led to increased public support for the law, which persists today.

KFF Health Tracking Poll: The Public's Views on the ACA

While President Trump failed in his first term to repeal the ACA, his administration repealed the individual mandate penalty, reduced federal funding for consumer assistance (navigators) by 84% and outreach by 90%, and expanded short-term insurance plans that can exclude coverage of preexisting conditions.

In a strange policy twist, the Trump administration ended payments to ACA insurers to compensate them for a requirement to provide reduced cost sharing for low-income patients. But, insurers responded by increasing premiums, which in turn increased federal premium subsidies and federal spending, likely strengthening the ACA.

Between President Trump’s presidential terms, the Biden administration restored outreach funding and signed legislation increasing the premium tax credits that help ACA Marketplace enrollees pay their premiums, leading to record enrollment and historically low uninsured rates.

The increased premium tax credits are set to expire at the end of 2025 unless Congress and President Trump take action. If these tax credits do expire, people purchasing subsidized coverage will face significant increases in their monthly premium payments and some may become priced out of the market.

President Trump’s second term has already brought federal policy changes that will significantly alter ACA Marketplace operations, consumer protections, and premium tax credit eligibility. Key changes in the 2025 budget reconciliation law, such as ending auto-renewals, removing repayment limits for tax credits when income rises, and tightening eligibility verification, are projected by the Congressional Budget Office (CBO) to result in 2 million people becoming uninsured.

Medicaid

Copy link to Medicaid

Since its establishment in 1965, Medicaid has evolved as states took up the optional joint federal-state program to the point that in the 1980s all 50 states were participating. Due to the nature of its federal and state management, there has been a give-and-take over the flexibility of and spending for the program, but it has generally expanded in its coverage of key population groups.

With the passage of the ACA, Medicaid experienced its largest federal policy coverage expansion with the addition of what was ultimately a state option to cover adults with incomes up to 138% of the federal poverty level in exchange for enhanced federal funding for the coverage. Much like the take-up of the original Medicaid program, states have gradually adopted the expansion so that only 10 states, mainly concentrated in the South, remain holdouts. However, recent federal actions may alter the expansion landscape.

Until 2025, the most serious attempt by federal policymakers to make cuts to the Medicaid program was during the 2017 failed attempt to repeal the ACA. Medicaid changes in the legislation included a rollback of enhanced federal matching funds for the Medicaid expansion and a per-enrollee cap of federal funds for most Medicaid enrollees. The 2025 budget reconciliation law includes the largest enacted cuts in Medicaid’s history, instituting Medicaid work requirements, tightening eligibility checks and reducing or capping types of provider funding. The CBO estimates that 7.5 million people will become uninsured due to the Medicaid provisions of the law. However, several of the Medicaid provisions will not be implemented until after the 2026 midterm elections.

Affordability of Health Care

Copy link to Affordability of Health Care

One persistent feature of health care as an election issue is that it is fundamentally an economic issue for the country and for individuals. If you are uninsured, you not only experience access issues, but also the high cost of health care treatment. If you have health insurance, you worry about annual premium changes, deductibles, and cost-sharing related to health care services and prescription drugs whose prices continue to rise.

President Trump has often spotlighted the high price of prescription drugs, criticizing both the pharmaceutical industry and pharmacy benefit managers. Although he kept the issue of drug prices on the political agenda as president, in the end, his first administration accomplished little to restrain them. 

President Biden signed the Inflation Reduction Act, which requires the federal government to negotiate the prices of certain drugs in Medicare, which was previously banned. How aggressively the prescription drug negotiation program proceeds during the second Trump administration is an open question. While President Trump has issued an executive order calling for a “most favored nation” policy for drug pricing, with prices in the U.S. matching the currently lower prices in other countries, it remains unclear how drug companies will respond to the call and whether there will be any enforcement mechanism.

Health Care Infrastructure of the Federal Government

Copy link to Health Care Infrastructure of the Federal Government

A feature of the second Trump administration has been the push to remake the executive branch of the federal government to reflect his priorities at a scale that hasn’t occurred in the recent past. Secretary of Health and Human Services (HHS), Robert F. Kennedy, Jr., announced a plan to restructure the department in March 2025 that would reduce the workforce substantially, create the new agency Administration for a Healthy America, reorganize and consolidate divisions and relocate offices.

HHS Secretary Kennedy is also leading the Make America Healthy Again (MAHA) Commission and making substantial changes to the vaccine approval process by remaking the roster for the Centers for Disease Control and Prevention’s Advisory Committee on Immunization Practices and having CDC change recommendations for who should receive the COVID-19 vaccine.

These changes to the federal health care infrastructure could impact the accessibility of vaccines and other preventive services, as well as undermine the confidence the public has in the government, particularly its scientific agencies.

Future Outlook

Copy link to Future Outlook

Ultimately, irrespective of the issues that get debated during the campaign, the outcome of federal elections – who controls the White House and Congress – has significant implications for the future direction of health care.

However, even with changes in party control of the federal government, generally incremental movement to the left or the right is the norm. Sweeping changes in health policy, such as the creation of Medicare and Medicaid or passage of the ACA, are rare in the U.S. political system and are usually preceded by one-party control of Congress and the presidency. More fundamental changes in health care financing and coverage, such as Medicare for All, face long odds. This is the case even though most of the public favors Medicare for All, though attitudes shift significantly after hearing messages about its potential impacts.

It has historically been politically difficult to take benefits away from people once they have them. That, and the fact that seniors are a strong voting bloc, has been why Social Security and Medicare have been considered political “third rails.” While Medicare and Social Security were largely untouched in the Republican tax and spending law passed in 2025, the law made substantial cuts to the ACA and Medicaid, and millions more people are projected to become uninsured in what will be the biggest rollback in federal support for health coverage ever. Looking toward the 2026 midterm election and beyond, changes to both the ACA and Medicaid, as well as fundamental changes to the health care infrastructure and public health policies of the federal government, may emerge as major campaign issues.

Resources

Copy link to Resources

Citation

Copy link to Citation

Levitt, L. & Singh, R., The Politics of Health Care and the 2024 Election. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/elections/health-policy-101-the-politics-of-health-care-and-elections/ (date accessed).