The U.S. Government and Global Health

Table of Contents

Introduction

Copy link to Introduction

While there is currently no standard, agreed-upon definition of global health, the National Academy of Medicine (formerly Institute of Medicine) defines global health as having “the goal of improving health for all people in all nations by promoting wellness and eliminating avoidable diseases, disabilities, and deaths.” A key dimension of global health is an emphasis on addressing inequities in health status between rich and poor countries and also for those who are most marginalized within countries, as well as a recognition that the health of people around the world is highly interconnected, with domestic and foreign health inextricably linked. 

The U.S. government has long been the largest donor to and implementer of global health programs in the world. These efforts have aimed to help improve the health of people in low- and middle-income countries while also contributing to broader U.S. global development goals, foreign policy priorities, and national security concerns, including helping safeguard the health of Americans. These efforts began decades ago and saw major expansion in the early part of the current century with the creation of the President’s Emergency Plan for AIDS Relief (PEPFAR) and other programs. Since the beginning of the second Trump administration, however, the U.S. global health response has undergone significant change, disruption, and retraction, and the global health landscape has been altered in fundamental ways. This has included, as part of a major review of U.S. foreign aid, the dissolution of the U.S. Agency for International Development (USAID), the main implementing agency for U.S. global health programs, the elimination of numerous programs and projects, and the transition of remaining programs to the State Department.  As part of its review, the administration is seeking to assess whether U.S. foreign aid programs are aligned with U.S. national interests.

What Is the U.S. Role in Global Health?

Copy link to What Is the U.S. Role in Global Health?

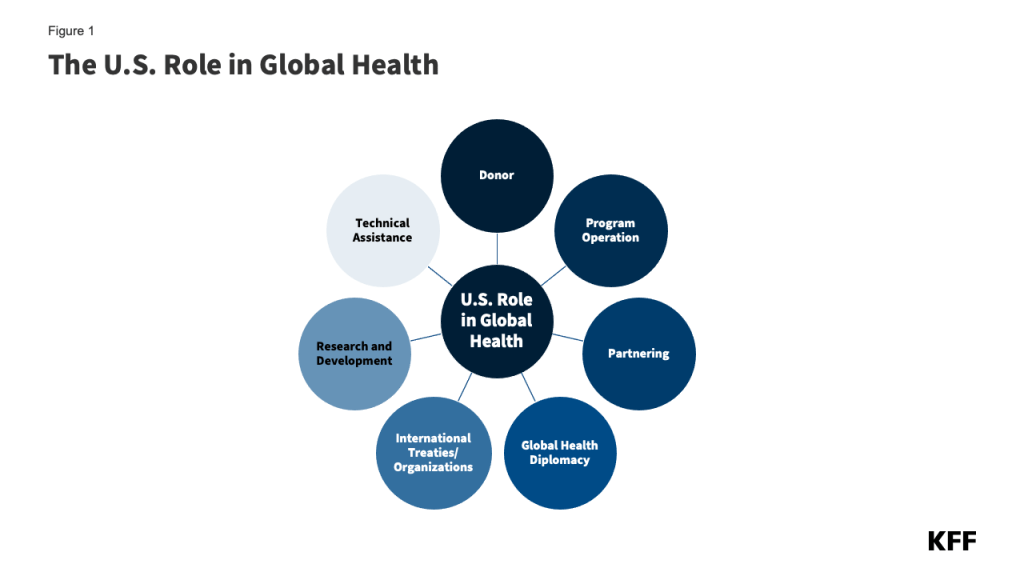
Historically, the U.S. role in global health is multifaceted and includes a broad range of activities. Its primary roles are as a supporter of bilateral (i.e., country-to-country) efforts, directly funding implementation of global health efforts in partner countries, and as a donor to multilateral health institutions (i.e., international organizations that pool support from multiple countries for one or more areas of global health). The U.S. also engages in global health diplomacy through its relationships with other governments, multilateral institutions, non-governmental organizations, and the private sector. Specifically, the U.S. government:

  • acts as a donor by providing financial and other health-related development assistance (e.g., commodities, like contraceptives or bed nets for protection from disease-carrying mosquitoes) to low- and middle-income countries;
  • operates programs and delivers health services;
  • provides technical assistance and other capacity-building support;
  • participates in major international health organizations and coordinates health efforts with other stakeholders through global health diplomacy;
  • conducts research;
  • supports international responses to disasters and other emergencies; and
  • partners with governments, non-governmental groups, and the private sector (Figure 1).

U.S. global health activities have targeted a variety of issues and used different intervention approaches such as:

  • Health services and systems strengthening: improving basic and essential health services, systems, and infrastructure;
  • Disease detection and response: supporting surveillance, prevention, and treatment of diseases, including both infectious (e.g., HIV, TB, malaria) and non-communicable diseases (e.g., cardiovascular disease, cancer);
  • Population and maternal/child health: promoting maternal health; reproductive health and family planning; child nutrition, immunization, and other child survival interventions;
  • Nutrition, water, and environmental health: providing non-emergency food aid and supporting dietary supplementation and food security; clean/safe water and sanitation; mitigation of environmental hazards; and
  • Research and development: investigating and developing new technologies, interventions, and strategies, including vaccines, medicines, and diagnostics.

What Are the Major Global Health Program Areas the U.S. Supports?

Copy link to What Are the Major Global Health Program Areas the U.S. Supports?

While the U.S. government’s involvement in global health currently faces an uncertain future – with a more limited scope, the dissolution of USAID, and cancelation of numerous U.S.-supported global health projects, as the Trump administration seeks to reorganize foreign aid more broadly –  the U.S. has historically supported global health through a wide array of bilateral and multilateral global health programs in countries around the world including:

HIV/PEPFAR

While the U.S. first provided funding to address the emerging global HIV epidemic in 1986, U.S. funding and attention for these efforts has grown significantly in the last two decades, particularly following President George W. Bush’s 2003 announcement of the President’s Emergency Plan for AIDS Relief (PEPFAR), the coordinated U.S. government response to global HIV. Now the largest commitment by any nation devoted to a single disease, the launch of PEPFAR led to substantially increased U.S. support for HIV prevention, treatment, and care efforts, as well as U.S. contributions to multilateral entities, including the Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund), the Joint United Nations Programme on HIV/AIDS (UNAIDS), and the International AIDS Vaccine Initiative (IAVI).  PEPFAR, which is housed in the Department of State, has been credited with saving 26 million lives and contributing to broader health, educational, and economic gains.  Currently, PEPFAR faces significant change. While U.S. policymakers had been increasingly looking at when and how to transition PEPFAR services and financing to country governments, the current Trump administration has sought to narrow PEPFAR’s scope and significantly accelerate this timeline. See the “Status of PEPFAR” fact sheet for more information.

Tuberculosis (TB)

Since the 1998 launch of USAID’s global TB control program, the U.S. response to global TB has expanded, particularly after 2003 when PEPFAR highlighted the U.S. government’s commitment to addressing TB. Prior to the current Trump administration, these efforts focused on diagnosis, treatment, and control of TB (including multi-drug-resistant and extensively drug-resistant TB, or MDR/XDR TB) as well as on research. The U.S. was also a donor to the Global Drug Facility of the Stop TB Partnership.  With the dissolution of USAID, remaining TB programming has been moved to the State Department and its scope has been reduced. See the “Status of U.S. Global Tuberculosis Efforts” fact sheet for more information.

Malaria/PMI

Engaged in malaria work since the 1950s, the U.S. supported expanded malaria efforts in low- and middle-income countries through the President’s Malaria Initiative (PMI), launched in 2005 and housed at and managed by USAID, as well as through research and other activities. PMI programs centered on expanding coverage of six key high-impact interventions to control or eliminate malaria, which included: diagnosis of malaria and treatment with artemisinin-based combination therapies (ACTs), entomological monitoring, intermittent preventive treatment in pregnancy (IPTp), indoor residual spraying (IRS) with insecticides, insecticide-treated mosquito nets (ITNs), and seasonal malaria chemoprevention (SMC). The U.S. has also supported the RBM Partnership to End Malaria.  Under the current administration, remaining PMI programming has been moved into the State Department. See the “Status of the President’s Malaria Initiative (PMI)” fact sheet for more information.

Maternal and Child Health (MCH)

Involved in efforts to improve MCH since the 1960s,  U.S. global MCH activities, which had been housed at and managed by USAID, aimed to bring to scale a range of high-impact interventions that mitigate maternal, newborn, and under-five deaths; prevent and address the indirect causes of such deaths (such as HIV, TB, and malaria); strengthen integration of maternal health services with family planning; improve equity of access to and use of services by vulnerable populations; and strengthen health systems. The U.S. has also been a donor to global organizations and initiatives addressing MCH, such as Gavi, the Vaccine Alliance, the United Nations Children’s Fund (UNICEF), and the Global Polio Eradication Initiative (GPEI).Under the current administration, remaining MCH programming has been moved into the State Department. See the “Status of U.S. Global Maternal and Child Health Efforts” fact sheet for more information.

Nutrition

For more than 40 years, the U.S. had been involved in nutrition efforts in low- and middle-income countries that aimed to prevent undernutrition through support for effective interventions, such as nutrition education, nutrition during pregnancy, exclusive breastfeeding, and micronutrient supplementation. Housed at and managed by USAID, U.S. global nutrition efforts were coordinated with the U.S. Feed the Future Initiative (FtF, launched in 2009), which aimed to address global hunger and food security. Currently, remaining nutrition programming has been moved to the State Department. See the “Status of U.S. Global Maternal and Child Health Efforts” fact sheet for more information.

Family Planning and Reproductive Health (FP/RH)

Engaged since the 1960s in international research on family planning and population issues as well as other FP/RH efforts (including the purchase and distribution of contraceptives in developing countries),  U.S. global FP/RH activities were designed to decrease the risk of unintended pregnancies and maternal and child mortality through effective interventions, including contraception, counseling, and post-abortion care. The U.S. also provided funding to global organizations addressing FP/RH, such as the United Nations Population Fund (UNFPA), though in some years, funding for UNFPA was withheld. The current administration has moved to end U.S. bilateral and multilateral support for family planning efforts. See the “Status of U.S. Family Planning and Reproductive Health Efforts” fact sheet for more information

Neglected Tropical Diseases (NTDs)

Having historically worked on addressing NTDs through research and surveillance, attention to and funding for U.S. global NTD efforts increased markedly in 2006 with the launch of the USAID NTD Program and the subsequent announcement of expanded efforts across the U.S. government in 2008. These efforts had focused on five NTDs (soil-transmitted helminths,  lymphatic filariasis or elephantiasis, onchocerciasis or river blindness, schistosomiasis or snail fever, and trachoma) that are responsible for the overwhelming majority of the NTD burden but can be controlled and even eliminated with low-cost and effective interventions, such as an integrated control approach targeting multiple NTDs simultaneously through mass drug administration (MDA). The future of NTD efforts is uncertain amid the current Trump administration’s foreign aid freeze and dissolution of USAID.

Global Health Security (GHS)

While the U.S. has supported global health security work for more than two decades, its involvement has expanded over time, with attention to these efforts growing significantly due to the COVID-19 pandemic. These efforts aimed to reduce the threat of emerging and re-emerging diseases by supporting preparedness, detection, and response capabilities worldwide. The U.S. had also played a key role in the development and 2014 launch of the “Global Health Security Agenda (GHSA).” Through this international partnership that now involves more than 70 countries and international organizations, the U.S. worked to help countries make measurable improvements in their GHS capabilities. The U.S. had also been a donor to the new Pandemic Fund, which seeks to provide sustained financing to help countries build their capacity to prevent, prepare for, and respond to epidemics and pandemics.  While the first U.S. global health security strategy had been developed by the first Trump administration, the current Trump administration has withdrawn this strategy, eliminated several global health security positions and some offices, and withdrawn from U.S. engagement in key international efforts. See the “Status of Global Health Security/Pandemic Preparedness” fact sheet for more information.

How Much Funding Does the U.S. Provide for Global Health?

Copy link to How Much Funding Does the U.S. Provide for Global Health?

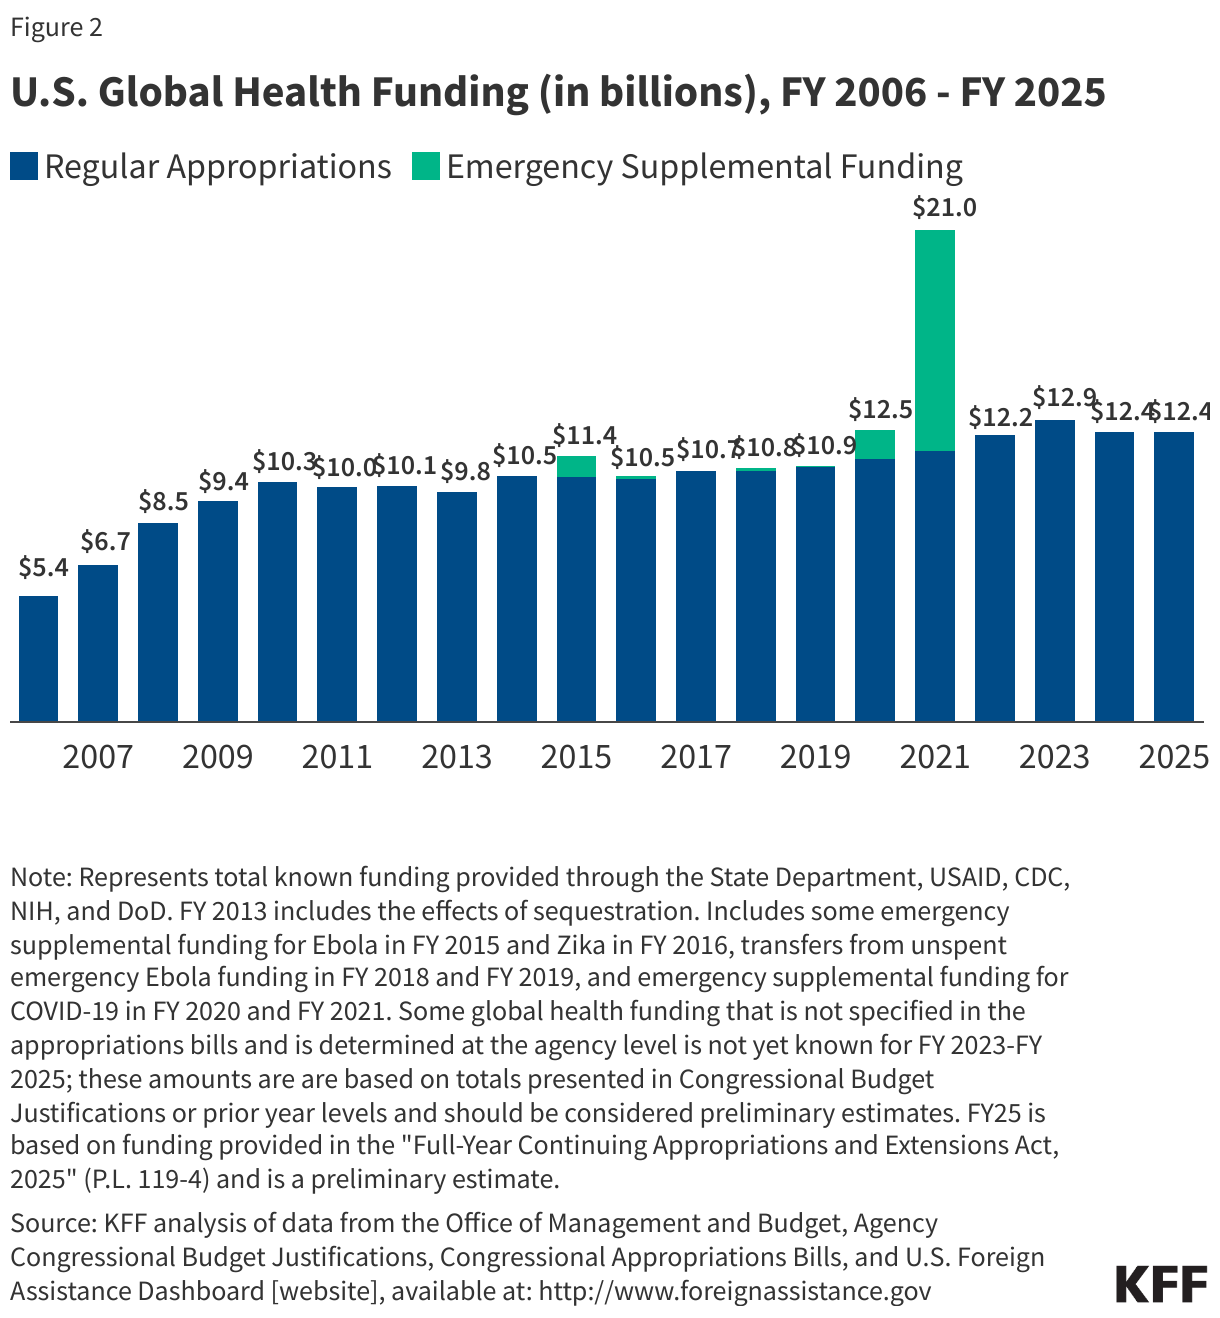
In FY 2025, U.S. funding appropriated by Congress for global health totaled $12.4 billion. While this funding has been appropriated to federal agencies, the current administration has withheld much of it from programming and sought to formally rescind (cancel) more than $1 billion in funding for global health, including some PEPFAR funding (Congress voted to amend the rescission package, reducing that amount to $500 million, and exempting PEPFAR and some other global health programs from cuts).  As such, funding amounts presented here for the current fiscal year may not reflect actual obligations or outlays of U.S. support. There is ongoing litigation federal court regarding these actions.

As Figure 2shows, U.S. appropriations for global health have grown significantly since the early 2000s, in large part due to funding for initiatives such as PEPFAR and PMI, but with spikes in some years due to emergency or supplemental funding for disease outbreaks such as Ebola, Zika, and COVID-19. Funding reached its highest level to date in FY 2021, largely due to the U.S. global response to the COVID-19 pandemic.

Although a large majority of the American public overestimates the share of the federal budget that is spent on foreign aid (with nearly half believing that the share is greater than 20%), U.S. foreign aid actually accounts for 1% or less of the federal budget, with U.S. funding for global health—which is part of the foreign affairs budget—accounting for an even smaller share.

U.S. Global Health Funding (in billions), FY 2006 - FY 2025

U.S. Global Health Funding by Program Area

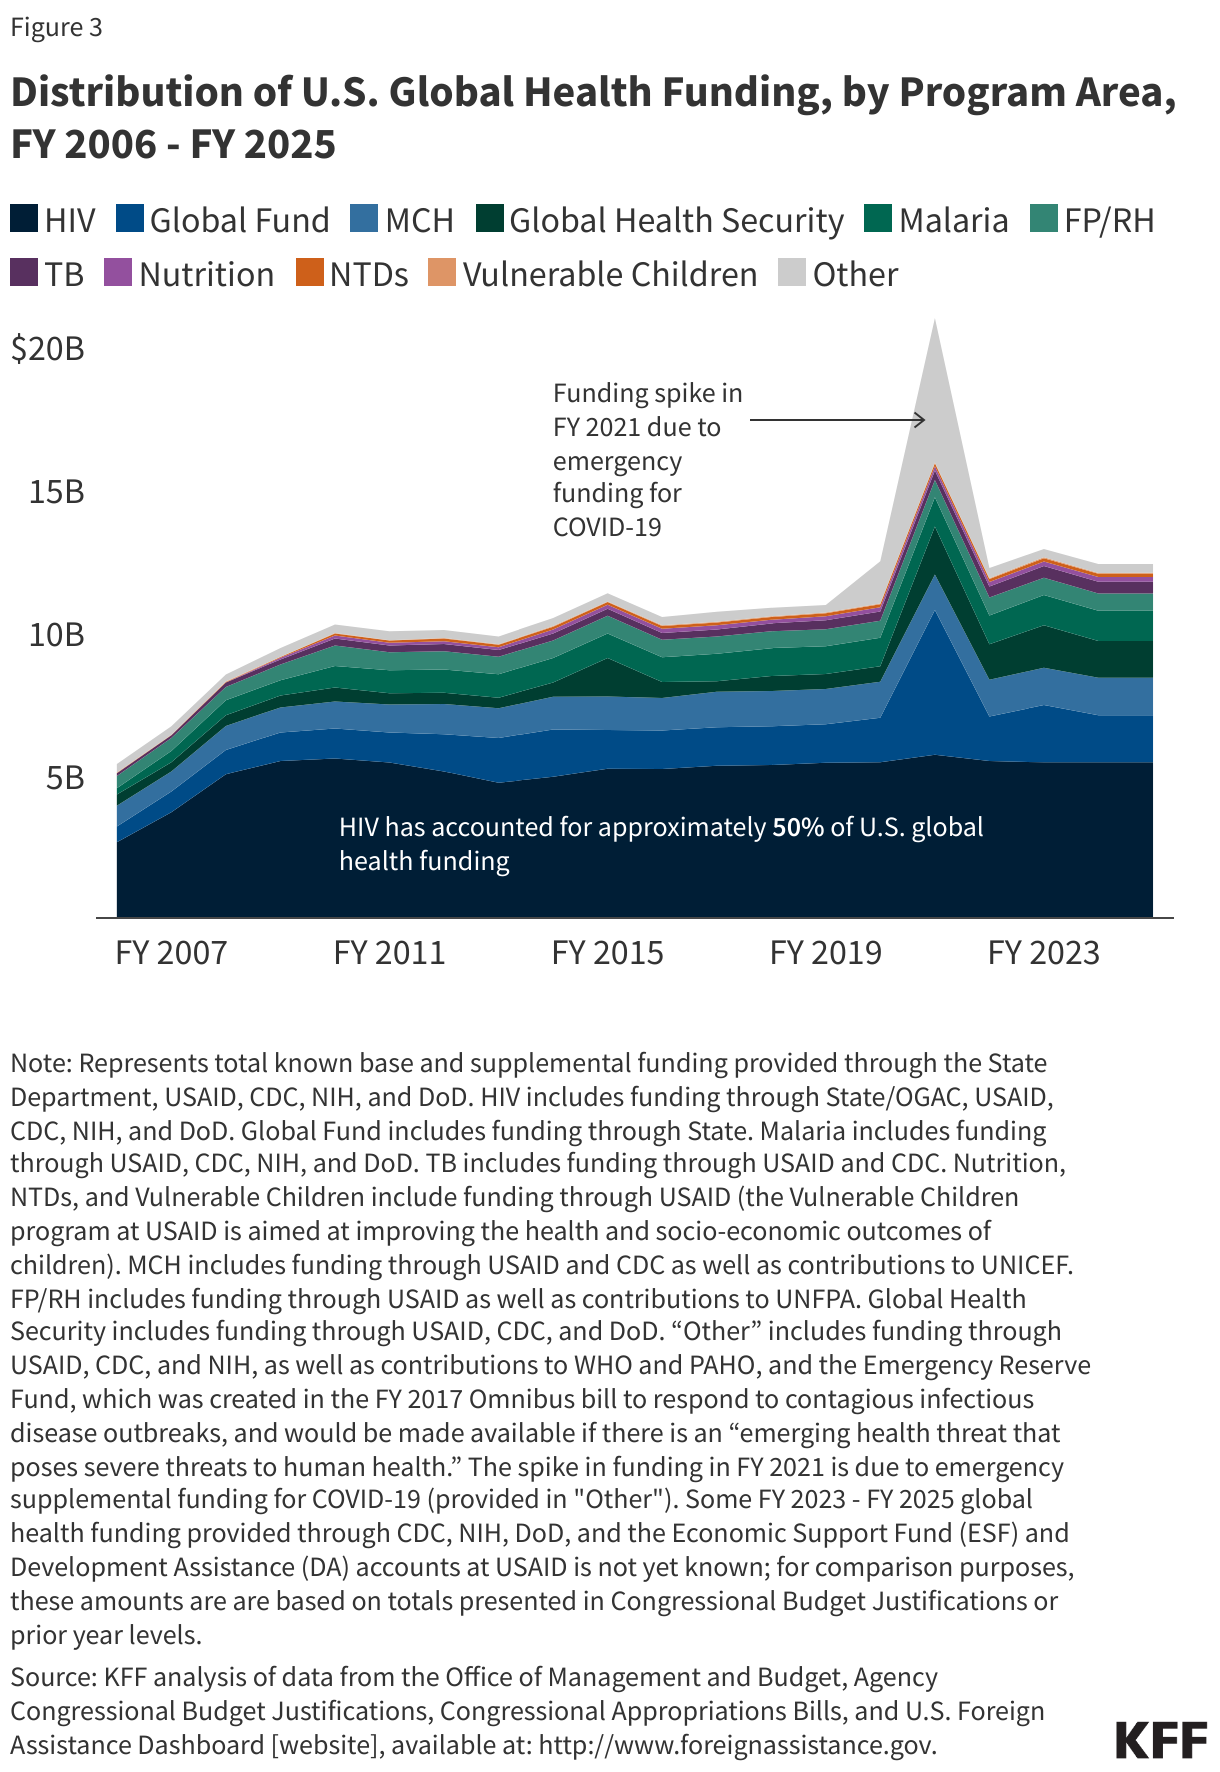
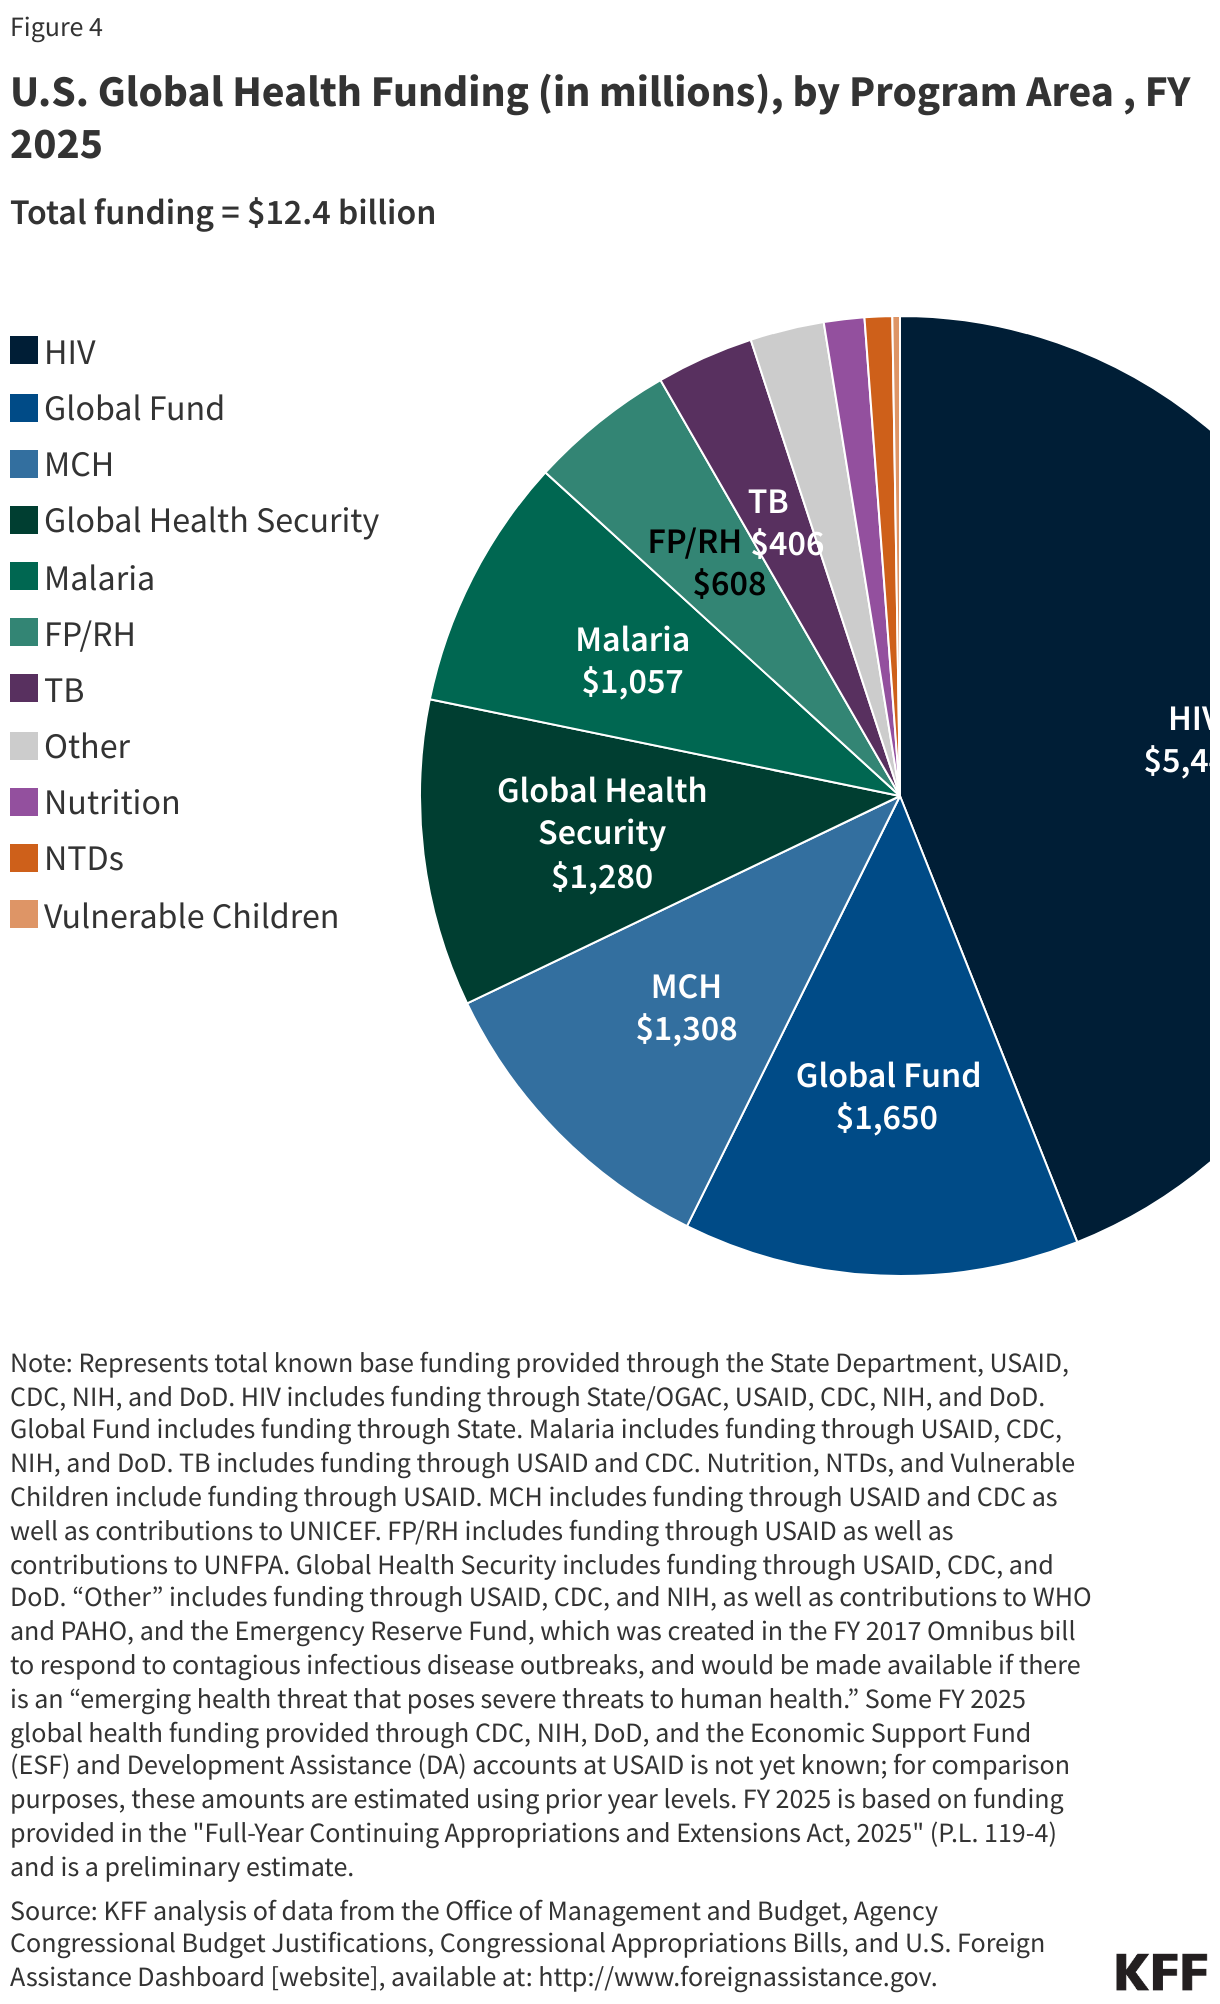
Looking across funding for the major global health program areas since FY 2006, most U.S. global health funding over time has been directed to HIV programs, accounting for approximately 50% of U.S. global health funding in most years (Figure 3). The Global Fund accounted for the next largest share over the period, followed by MCH and malaria. More recently, the U.S. has emphasized global health security more, with funding for these efforts increasing considerably during the COVID-19 pandemic and afterward. Consistent with this trend, most funding was provided to HIV efforts ($5.4 billion or 44%), followed by the Global Fund ($1.7 billion or 13%) and maternal and child health and global health security (both $1.3 billion or 10%) in FY 2025 (Figure 4).

Distribution of U.S. Global Health Funding, by Program Area, FY 2006 - FY 2025
U.S. Global Health Funding (in millions), by Program Area , FY 2025

Bilateral vs. Multilateral Aid

Most U.S. global health funding is provided bilaterally – that is, funding provided by the U.S. directly to or on behalf of a recipient country or region. In FY 2025, about 80% of the U.S. global health budget was provided through bilateral programs. The remainder (about 20%) is provided multilaterally through U.S. contributions to international institutions and organizations (see “What Multilateral Health Organizations Are Supported by the U.S.?”).

Which U.S. Agencies Are Involved in Carrying Out Efforts in These Program Areas?

Copy link to Which U.S. Agencies Are Involved in Carrying Out Efforts in These Program Areas?

Historically, the U.S. government’s engagement in global health has been carried out and overseen by multiple executive branch departments and agencies and the legislative branch, including several congressional committees (Figure 5). The current administration has made significant changes to this infrastructure. See the “Proposed Reorganization of U.S. Global Health Programs” fact sheet for more information.

Executive Branch

In general, U.S. global health engagement has developed within two main structures of the Executive Branch of government: the foreign assistance structure, which is predominantly global development-oriented and has close links to foreign policy; and the public health structure, which has its roots in disease prevention, control, and surveillance efforts.

Most funding for and oversight of U.S. global health resides within the foreign assistance structure, including:

  • Department of State (State): Established in 1789, the Department of State is the Cabinet-level foreign affairs agency of the United States. It advances U.S. objectives and interests worldwide through its primary role in developing and implementing the President’s foreign policy. Prior to the current Trump administration, it also provided policy direction to USAID, the lead federal agency for development assistance. The Trump administration has dissolved USAID and moved remaining global health activities into the Department of State. The Department of State’s Bureau for Global Health Security and Diplomacy (GHSD) coordinates the Department’s work on global health security, including HIV, and houses PEPFAR.
  • U.S. Agency for International Development (USAID): Established in 1961, USAID was an independent U.S. federal government agency that received overall foreign policy guidance from the Secretary of State. Its role was to support long-term and broad-based economic growth in countries and advance U.S. foreign policy objectives by supporting activities through each of its programmatic functional bureaus (e.g., Bureau for Global Health) and regional bureaus. Most USAID global health programs had been coordinated through the Bureau for Global Health, including HIV and other infectious diseases, MCH, nutrition, FP/RH, NTDs, and global health security. USAID has now been dissolved by the current administration.  
  • Millennium Challenge Corporation (MCC): Established in 2004, MCC administers the Millennium Challenge Account (MCA), a U.S. government initiative providing development assistance to eligible countries to promote economic growth and reduce poverty in low- and middle-income countries. Although MCC supports several health-related programs, health is not the main focus or purpose of its work; its design is intended to link MCC contributions for development assistance (to reduce poverty through support for economic growth) to greater responsibility by low- and middle-income countries for successfully attaining certain governance and development benchmarks. The current Trump administration had sought to close down the agency but ultimately did not do so.

Agencies within the public health structure operate global health programs directly or in conjunction with foreign assistance agencies. They are represented most prominently by several agencies within the Department of Health and Human Services (HHS), including:

  • Office of Global Affairs (OGA): OGA’s primary function is global health diplomacy – particularly coordinating and maintaining engagement across HHS and the U.S. government with foreign governments and ministries of health, multilateral organizations, civil society groups, and the private sector – exchanging best practices and sharing technical knowledge to advance U.S. global health priorities and research.
  • Centers for Disease Control and Prevention (CDC): With a long history of working on international health issues, prior to the current Trump administration, CDC focused on disease control and prevention and health promotion through operations, development assistance, basic and field research, technical assistance, training/exchanges, and capacity building. The current administration has eliminated many of the staff working on these issues and sought to eliminate the CDC’s global health center.
  • National Institutes of Health (NIH): One of the world’s leading research entities on global health, NIH conducts biomedical and behavioral science research on diseases and disorders to enhance diagnosis, prevention, and treatment and provides technical assistance and training. Prior to the current Trump administration, all 27 of the agency’s institutes and centers engaged in global health activities, but these activities are already being curtailed or eliminated.
  • Food & Drug Administration (FDA): The FDA screens pharmaceutical and biological products for safety and efficacy and helps oversee the safety of the U.S. food supply.
  • Health Resources and Services Administration (HRSA): HRSA builds human and organizational capacity and promotes health systems strengthening to deliver care in PEPFAR countries.

In addition to the foreign assistance and public health service agencies, other departments and agencies involved in global health have included the Department of Defense (DoD), the Department of Agriculture (USDA), the Peace Corps, the Environmental Protection Agency (EPA), the Department of Homeland Security (DHS), the Department of Labor (DoL), the Department of Commerce (Commerce), the Office of the U.S. Trade Representative (USTR), and the National Security Council (NSC). The NSC, which sits within the White House, plays a significant role across the U.S. government, as it is responsible for coordinating and reviewing the U.S. strategy and activities related to global health security, including its international response. However, the administration has eliminated many of the staff working on these issues, and is no longer operating the White House Office of Pandemic Preparedness and Response (OPPR), which had been responsible for domestic policy coordination related to health security.

Legislative Branch

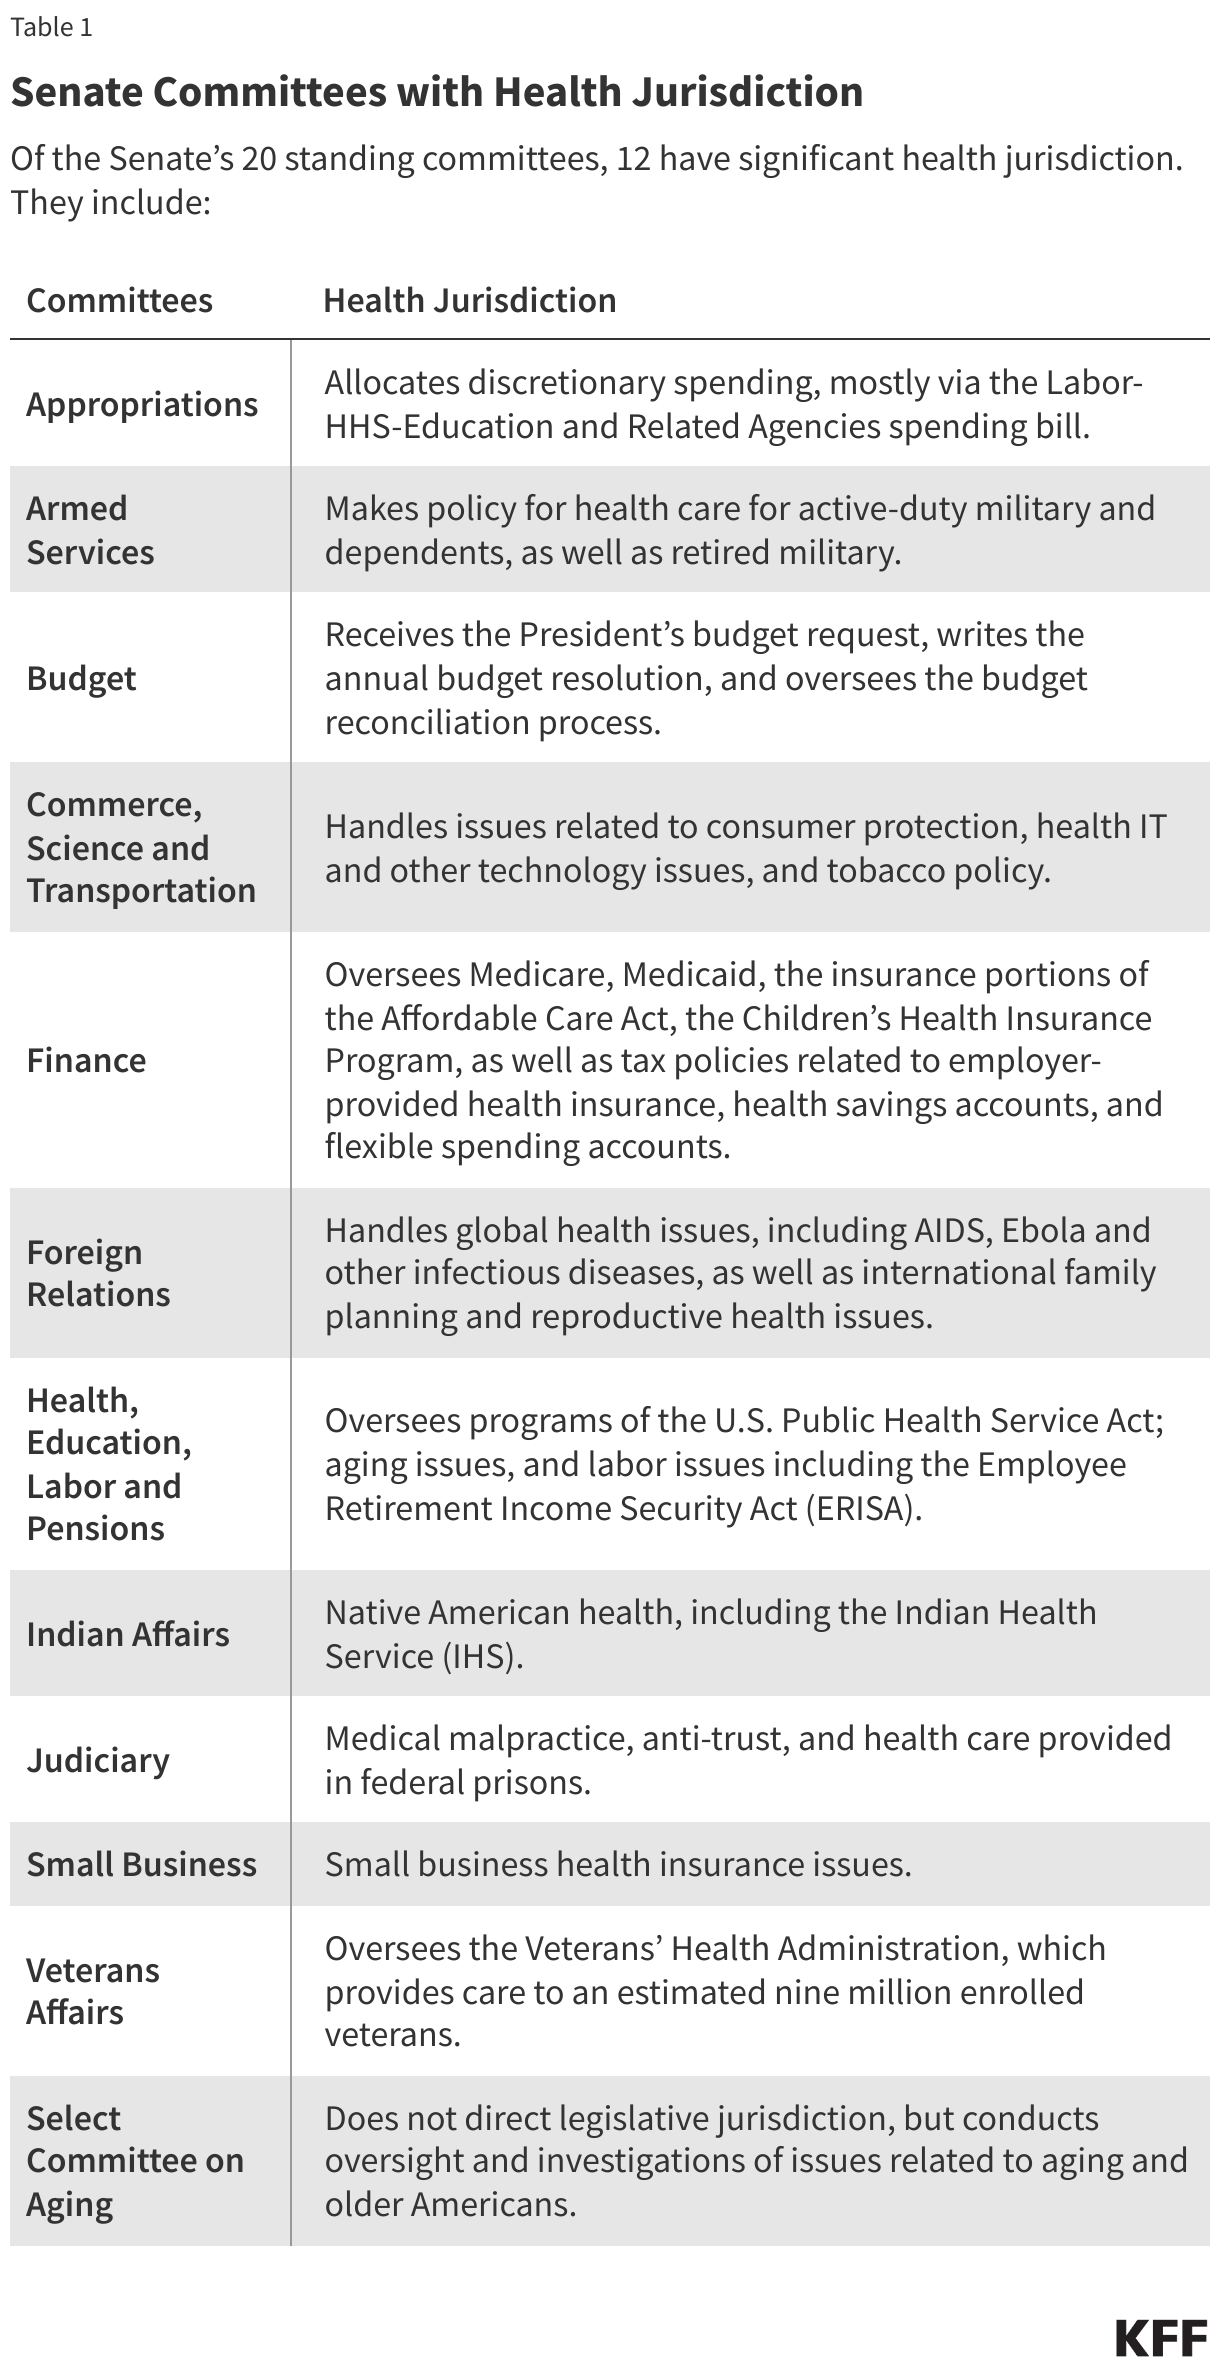
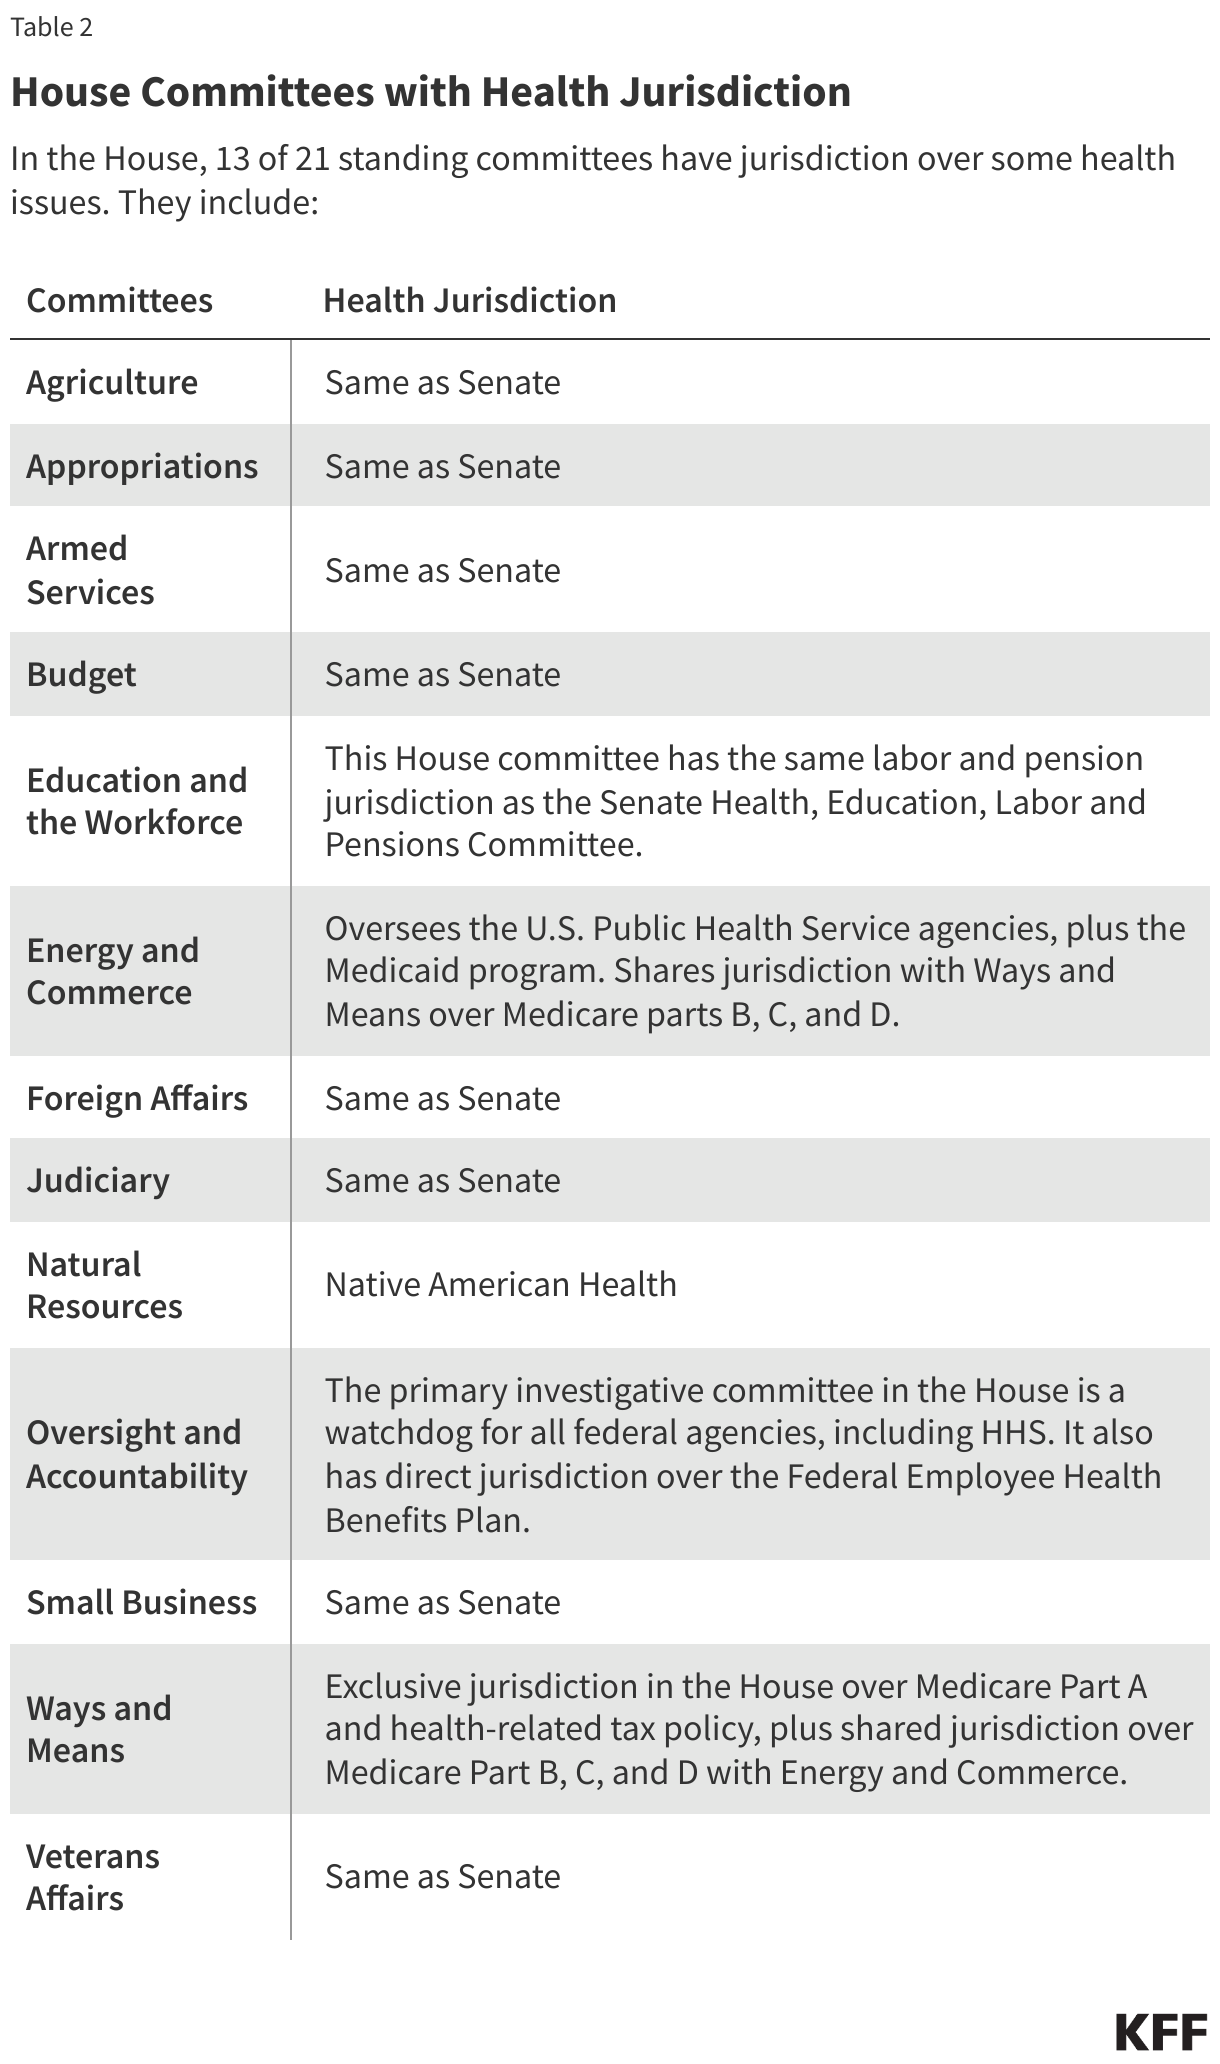
The U.S. Congress introduces, considers, and passes global health-related legislation; oversees global health efforts, specifying how funds for these programs are to be (and not to be) spent; authorizes and appropriates funding; and confirms presidential appointees to key U.S. global health positions. Major committees of the House of Representatives (House) and Senate with jurisdiction over global health efforts include: the House Committee on Foreign Affairs, Senate Committee on Foreign Relations, House Committee on Energy and Commerce, Senate Committee on Health, Education, Labor, and Pensions, and the Senate and House Appropriations Committees.

The U.S. global health response has been defined by numerous governing statutes, authorities, and policy decisions. For instance, the legislation that created PEPFAR in 2003 and its subsequent reauthorizations in 2008, 2013, 2018, and 2024 are key statutes of U.S. global health policy, as they govern its bilateral HIV response, bilateral assistance for TB and malaria, and participation in the Global Fund. Other statutory requirements that shape the implementation and scope of U.S. global health activities are those governing U.S. global FP/RH efforts, such as those directing how U.S. funds may not be spent. For instance, the Helms Amendment (1973) prohibits the use of foreign assistance to pay for the performance of abortion as a method of family planning or to motivate or coerce any person to practice abortion. The Kemp-Kasten Amendment (1985) prohibits funding any organization or program, as determined by the President, that supports or participates in the management of a program of coercive abortion or involuntary sterilization (it has been invoked at times to restrict funding to UNFPA).

While Congress has authority over many aspects of global health, the current administration has taken several actions without its direct consent (such as eliminating USAID and withholding Congressionally-directed appropriations), and has questioned the extent of Congressional authority in these areas. It is unclear if Congress will act on these issues and some of these questions are being litigated in federal court.

Where Do U.S. Bilateral Global Health Programs Operate?

Copy link to Where Do U.S. Bilateral Global Health Programs Operate?

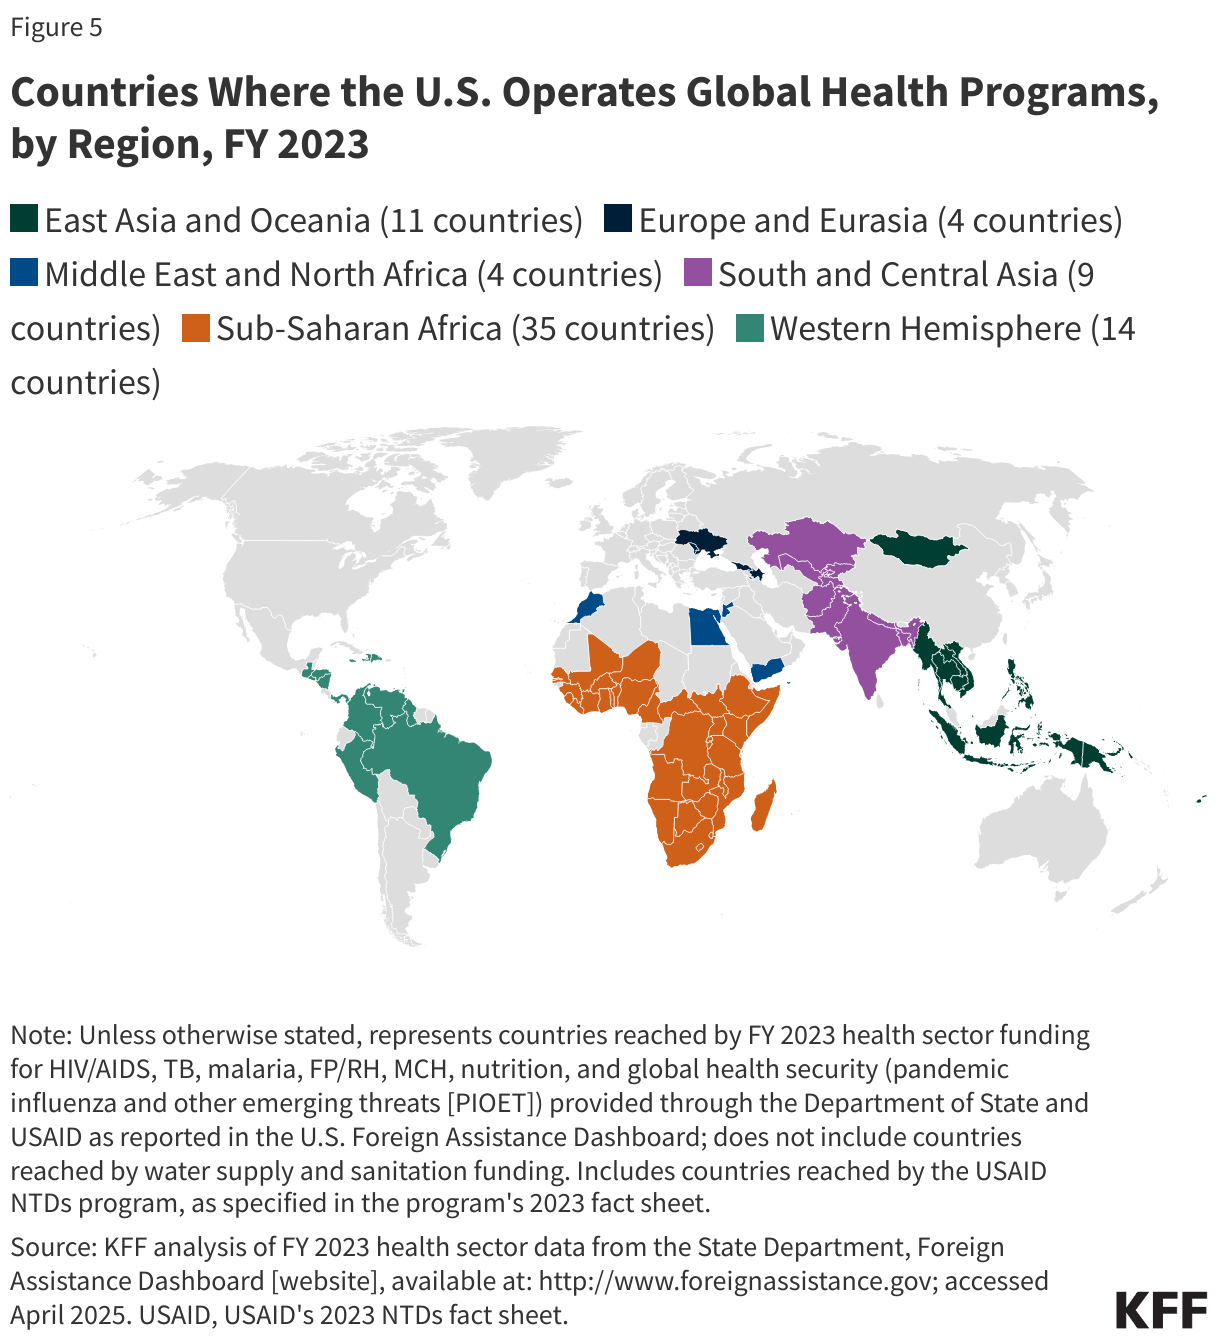
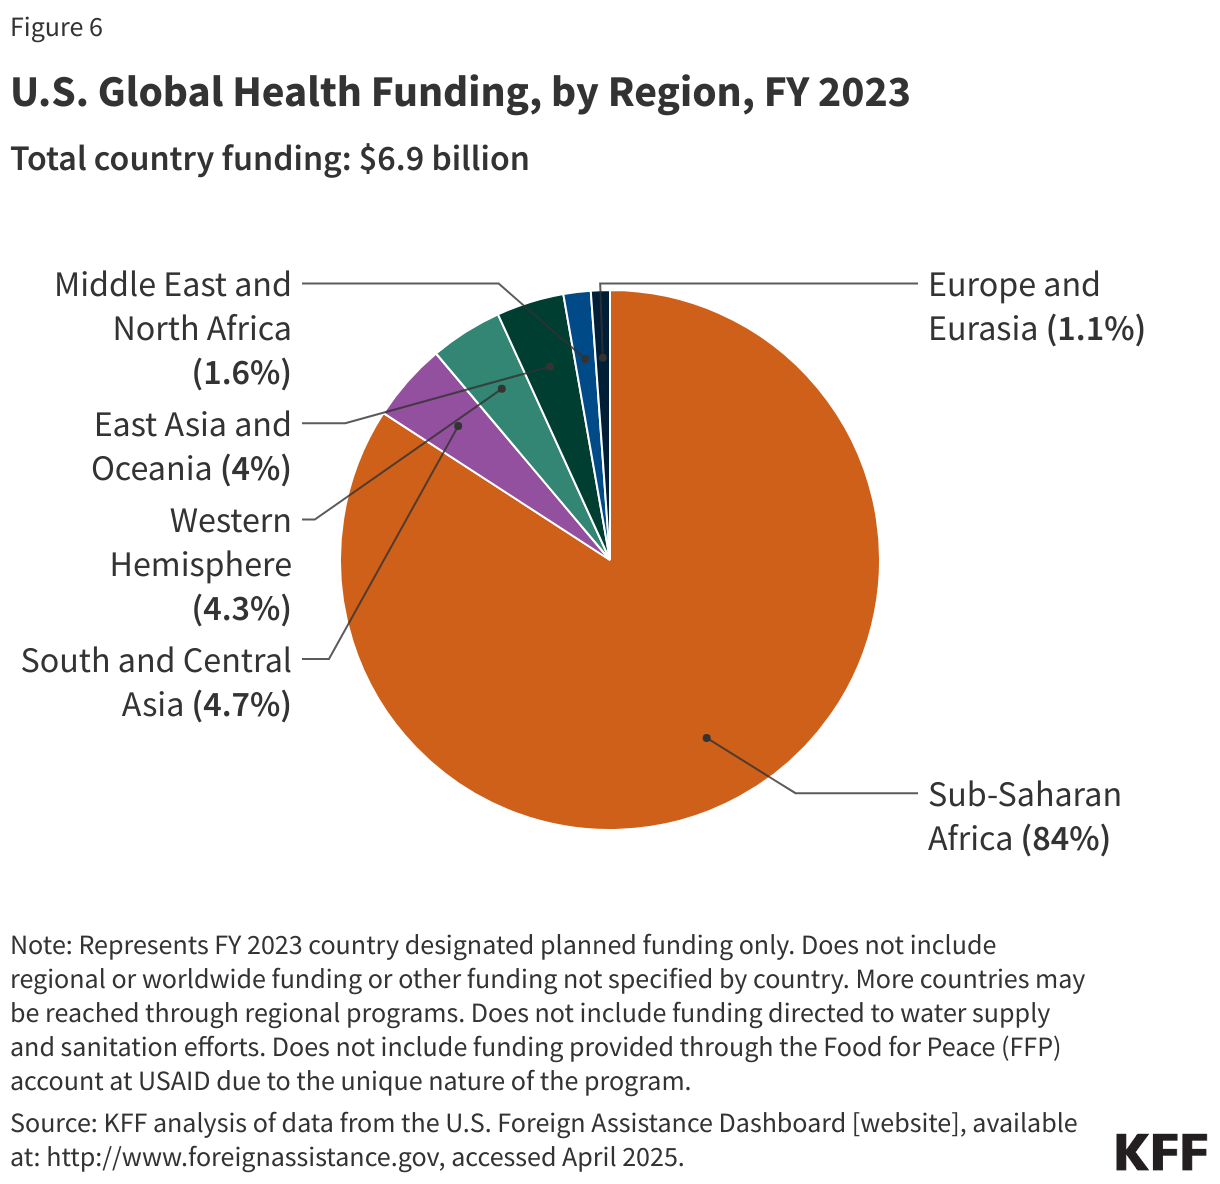
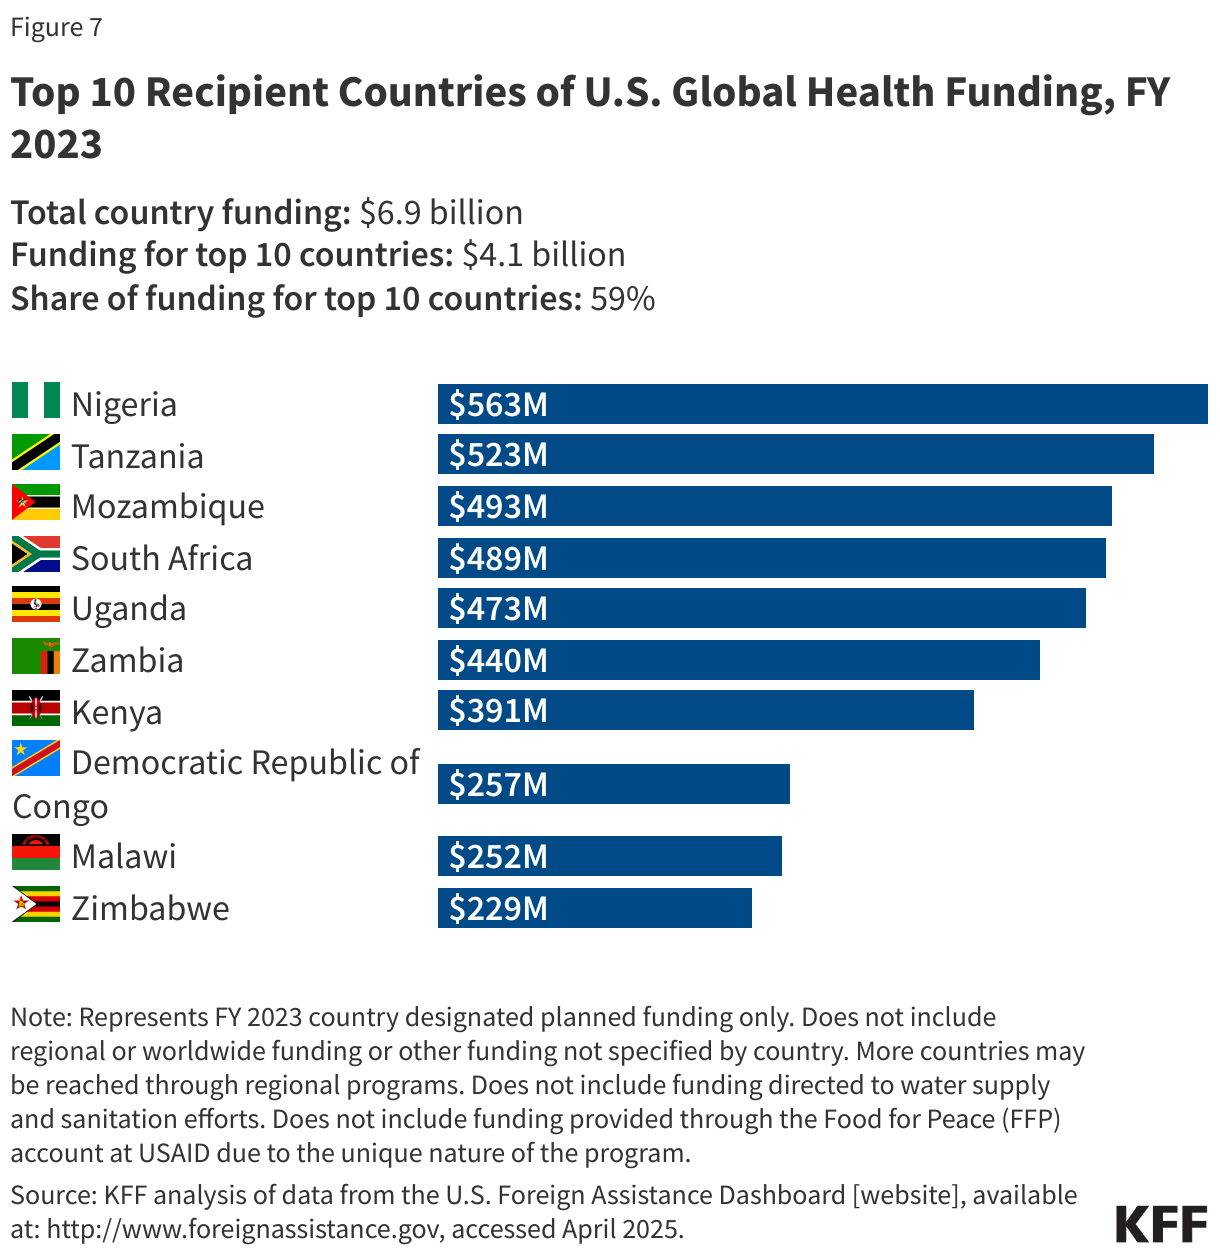
Prior to the current Trump administration, the U.S. provided bilateral support for U.S. global health programs in almost 80 countries, with additional countries reached through U.S. regional global health programs and U.S. contributions to multilateral organizations. Multiple factors determined where the U.S. channeled its global health support. While more U.S. support was generally directed to countries facing a higher burden of disease, it was also influenced by factors such as the presence of willing and able partner governments, a history of positive relations and goodwill with host countries, strategic and national security priorities, and funding and personnel availability. The majority of countries receiving U.S. bilateral support for global health (“partner countries”) were located in sub-Saharan Africa (35 countries), followed by the Western Hemisphere (14 countries), East Asia and Oceania (11 countries), South and Central Asia (9 countries), Europe and Eurasia (4 countries), and Middle East and North Africa (4 countries) (Figure 5). Most U.S. bilateral support for global health programs was provided in sub-Saharan Africa (84%) (Figure 6). Furthermore, the top 10 country recipients of U.S. global health funding, representing 59% of U.S. bilateral support for global health, were all in this region (Figure 7).

Countries Where the U.S. Operates Global Health Programs, by Region, FY 2023
U.S. Global Health Funding, by Region, FY 2023
Top 10 Recipient Countries of U.S. Global Health Funding, FY 2023

The U.S. typically operated more than one health program (HIV, TB, malaria, etc.) in each partner country. While in most countries, the U.S. operated programs in four or fewer global health areas, this number was generally higher in countries in sub-Saharan Africa (five or more).

What Multilateral Health Organizations Are Supported by the U.S.?

Copy link to What Multilateral Health Organizations Are Supported by the U.S.?

In addition to its bilateral programs, the U.S. has a long history of engagement with multilateral health organizations and international institutions, beginning with its role in the development of the first such organizations, including the Pan-American Health Organization (PAHO) in the early 1900s and the World Health Organization (WHO) a few decades later. This involvement continued with, for example, the Global Fund (which the U.S. helped to launch in 2001), Gavi (launched in 2000), the GHSA (which the U.S. played a key role in developing and launching in 2014), and the Pandemic Fund (launched in 2022). Prior to the current Trump administration – which is carrying out a review of its engagement in international organization to determine the future of U.S. multilateral participation and support – U.S. support for multilateral global health efforts has taken various forms, including:

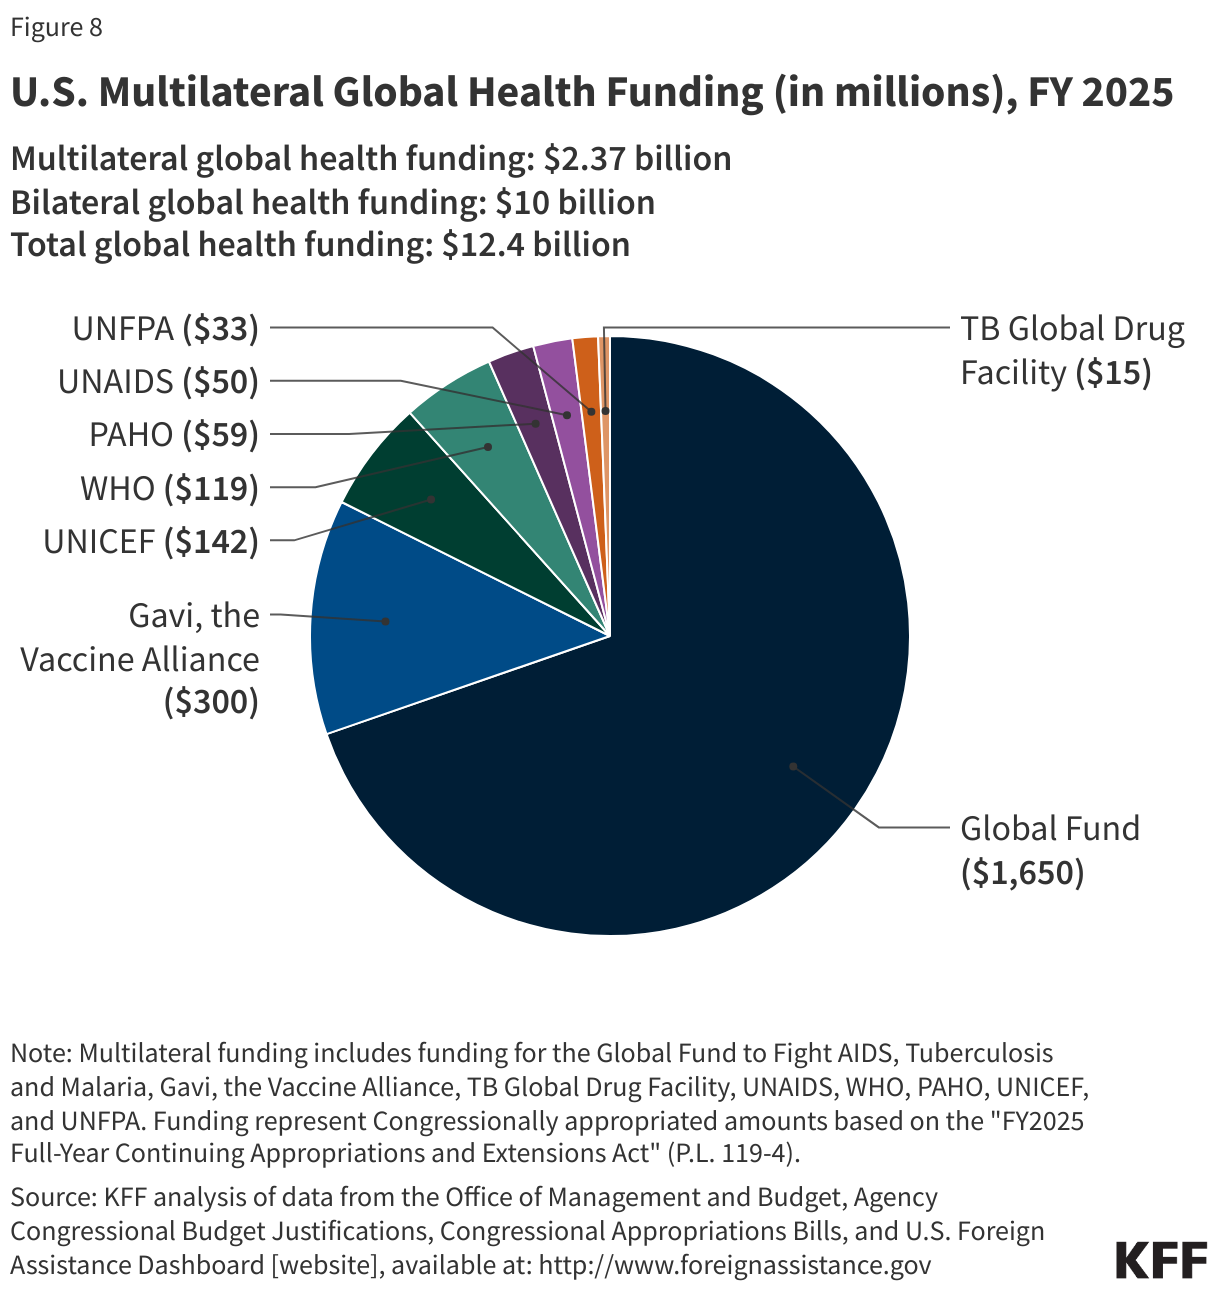
  • Funding. The U.S. has often been the largest or one of the largest donors to multilateral health efforts, funding core (generally used to support essential functions and operations) and voluntary (used for specific projects or initiatives the U.S. seeks to support) contributions. About a fifth (19%) of U.S. global health funding supported U.S. contributions to multilateral health organizations (Figure 8). However, some global health support to multilateral organizations has already been reduced or eliminated by the current Trump administration, such as funding and engagement in the World Health Organization, UNFPA, and the Pandemic Fund.
  • Governance. The U.S. has been active in the governance structures that oversee multilateral global health organizations and initiatives, including holding permanent or rotating seats on many of their boards.
  • Technical assistance. The U.S. has offered technical assistance in support of grants to partner countries, providing additional staff capacity to international organizations (by detailing U.S. government employees to these organizations for periods of time).
  • Standard setting. The U.S. has engaged in standard-setting, weighing in on global plans, treaties, and agreements to respond to a range of health issues as they are developed and considered for approval by the larger body.
U.S. Multilateral Global Health Funding (in millions), FY 2025

The U.S. has engaged with a number of multilateral global health organizations, including health-focused specialty agencies of the United Nations (U.N.) and international financing mechanisms for global health. Key among these are eight to which Congress specifically directs funding (though the U.S. also reaches other multilateral health institutions without direct Congressional appropriations but rather through general support), of which the U.S. has been the top contributor to five (the Global Fund, PAHO, UNAIDS, UNICEF, and WHO):

U.N. Agencies

  • World Health Organization (WHO): WHO, created in 1948, is the directing and coordinating authority for health within the U.N. system. WHO provides international leadership on global health matters, shaping the health research agenda, setting norms and standards, providing technical support to countries, and monitoring and assessing health trends. The U.S. has been involved in WHO since its creation, providing financial and technical support as well as participating in its governance structure. However, President Trump announced on the first day of his second term that the U.S. would withdraw as a member of WHO and halt funding to the organization.
  • Pan American Health Organization (PAHO): PAHO is the oldest international health agency, founded originally as the International Sanitary Bureau in 1902. The U.S. joined PAHO as a member state in 1925. PAHO, the specialized international health agency for the Americas, “works with countries throughout the region to improve and protect people's health” and serves as the WHO Regional Office for the Americas and as the health organization of the inter-American System.
  • Joint United Nations Programme on HIV/AIDS (UNAIDS): UNAIDS, created in 1996 as the successor organization to the WHO Global Programme on AIDS (GPA), is the leading global organization for addressing HIV/AIDS. Coordinating efforts across the U.N. system, it is made up of 11 U.N. co-sponsors and guided by a Programme Coordinating Board (PCB), which is a subset of its co-sponsors and government representatives. The U.S. currently serves on the PCB.
  • United Nations Children’s Fund (UNICEF): UNICEF, created in 1946, aims to improve the lives of children, particularly the most disadvantaged children and adolescents, and is one of the largest purchasers of vaccines worldwide. The U.S. was a founding member that same year.
  • United Nations Population Fund (UNFPA): UNFPA, created in 1969, is the largest purchaser and distributor of contraceptives worldwide. While the U.S. helped to found UNFPA and was a leading supporter for many years, its support has fluctuated significantly and sometimes been withheld entirely over the years, due to ongoing U.S. political debates about abortion. The Trump administration has announced that it is withholding funding from UNFPA.

Non-U.N. Financing Mechanisms

  • Gavi, the Vaccine Alliance (Gavi): Gavi, created in 2000, is a public-private partnership that aims to increase access to immunization in poor countries. The U.S. has been involved in Gavi since its creation through contributions, participation in Gavi’s governance, and technical assistance. The U.S. is the second largest donor to Gavi’s core programs and the top donor to Gavi’s COVAX Advance Market Commitment (COVAX AMC), a financial mechanism within COVAX that supports low- and middle-income countries through procurement and distribution of COVID-19 vaccines.
  • Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund): The Global Fund, created in 2001, is an independent multilateral financing entity that supports HIV, TB, and malaria programs in low- and middle-income countries. The U.S. was involved in creating the Global Fund and maintains a permanent seat on its Board. U.S. contributions and those of other donors are pooled and then provided by the Global Fund to country-driven projects based on technical merit and need.
  • TB Global Drug Facility: The Global Drug Facility, created in 2001, is a financing mechanism of the Stop TB Partnership; it provides grants to countries for TB drugs.

U.S. support for multilateral institutions overall has fluctuated over time, reflecting, in part, changing U.S. leadership views on the relative value of bilateralism versus multilateralism. As a result, U.S. engagement in and contributions to specific multilateral health organizations and institutions may change over time. For example, the U.S. under the first Trump administration did not participate in the partnership to create  COVAX (an international partnership led by the Coalition for Epidemic Preparedness Innovations [CEPI], Gavi, and WHO) to facilitate greater global access to the COVID-19 vaccine, although Congress did provide $4 billion in emergency funding to Gavi in support of COVID-19 vaccine access. Under the Biden administration, the U.S. joined the COVAX partnership.

Multilateral initiatives complement U.S. bilateral global health efforts, helping make progress toward U.S. goals in various program areas. In some cases, U.S. multilateral global health support allows the U.S. to reach a larger number of countries; it also may help to leverage additional funding and provide opportunities for improved coordination and technical consultations. Additionally, U.S. policies related to funding can greatly influence other financial support for multilaterals. For instance, since U.S. law has required that the U.S. contribution to the Global Fund cannot exceed 33% of total contributions from all donors, the U.S. contribution has leveraged other donor contributions; in effect, this requirement encouraged increased support from other donors and prevented the U.S. from becoming the predominant donor to the Global Fund.

How Does the U.S. Compare to Other Donors of International Health Assistance?

Copy link to How Does the U.S. Compare to Other Donors of International Health Assistance?

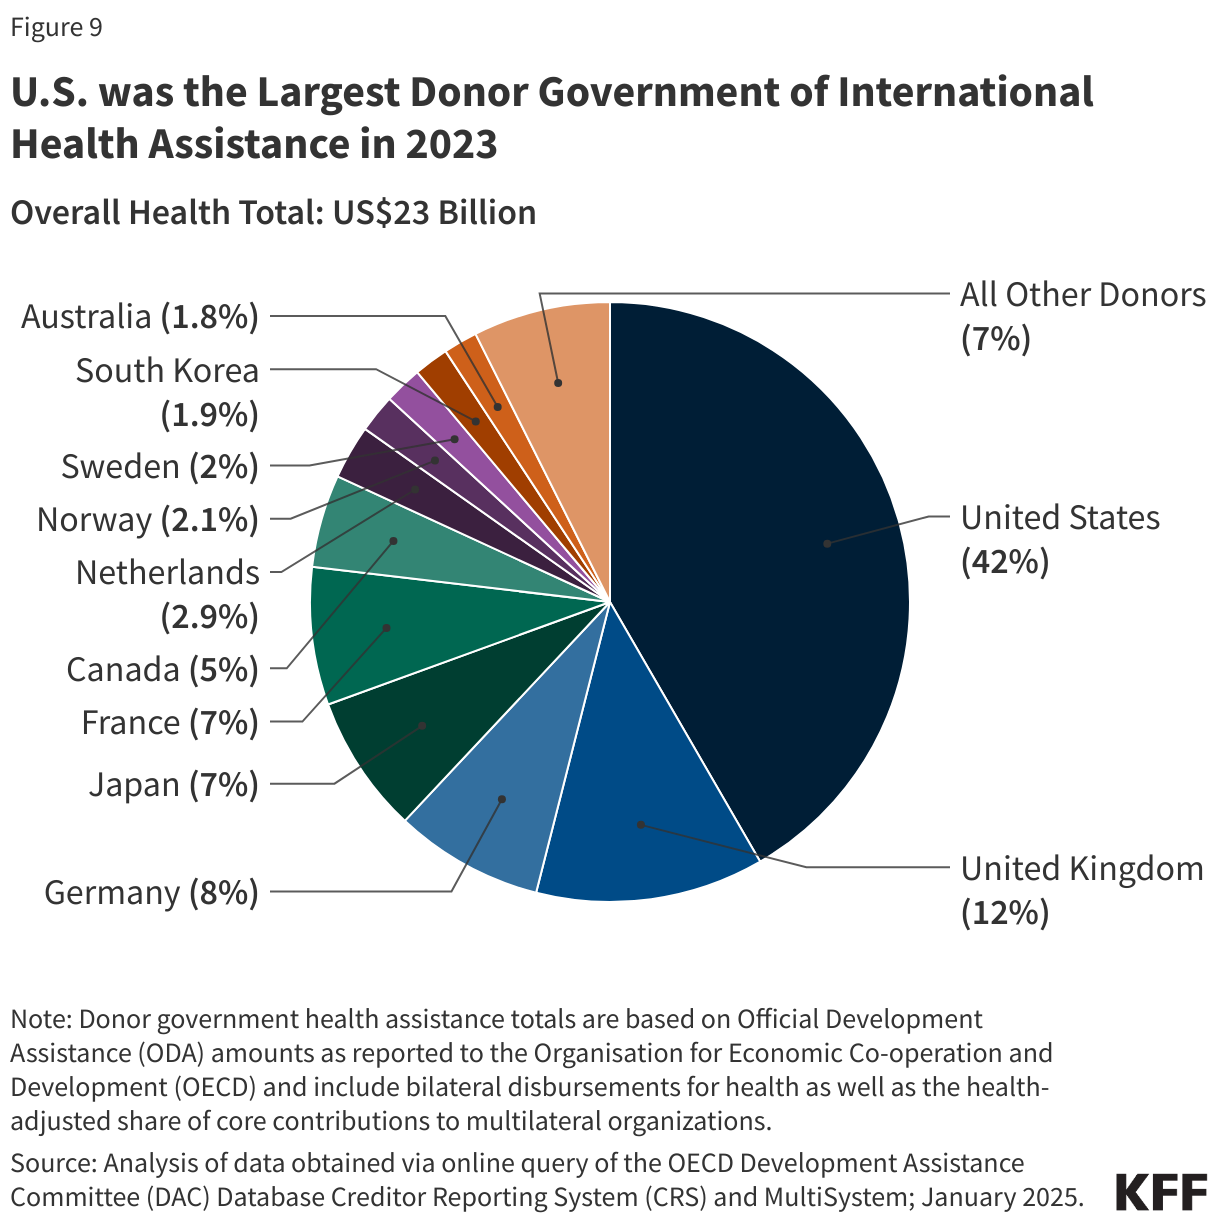
The U.S. has been the largest donor to global health, providing over 40% of all international health assistance among major donor governments (Figure 9).

U.S. was the Largest Donor Government of International Health Assistance in 2023

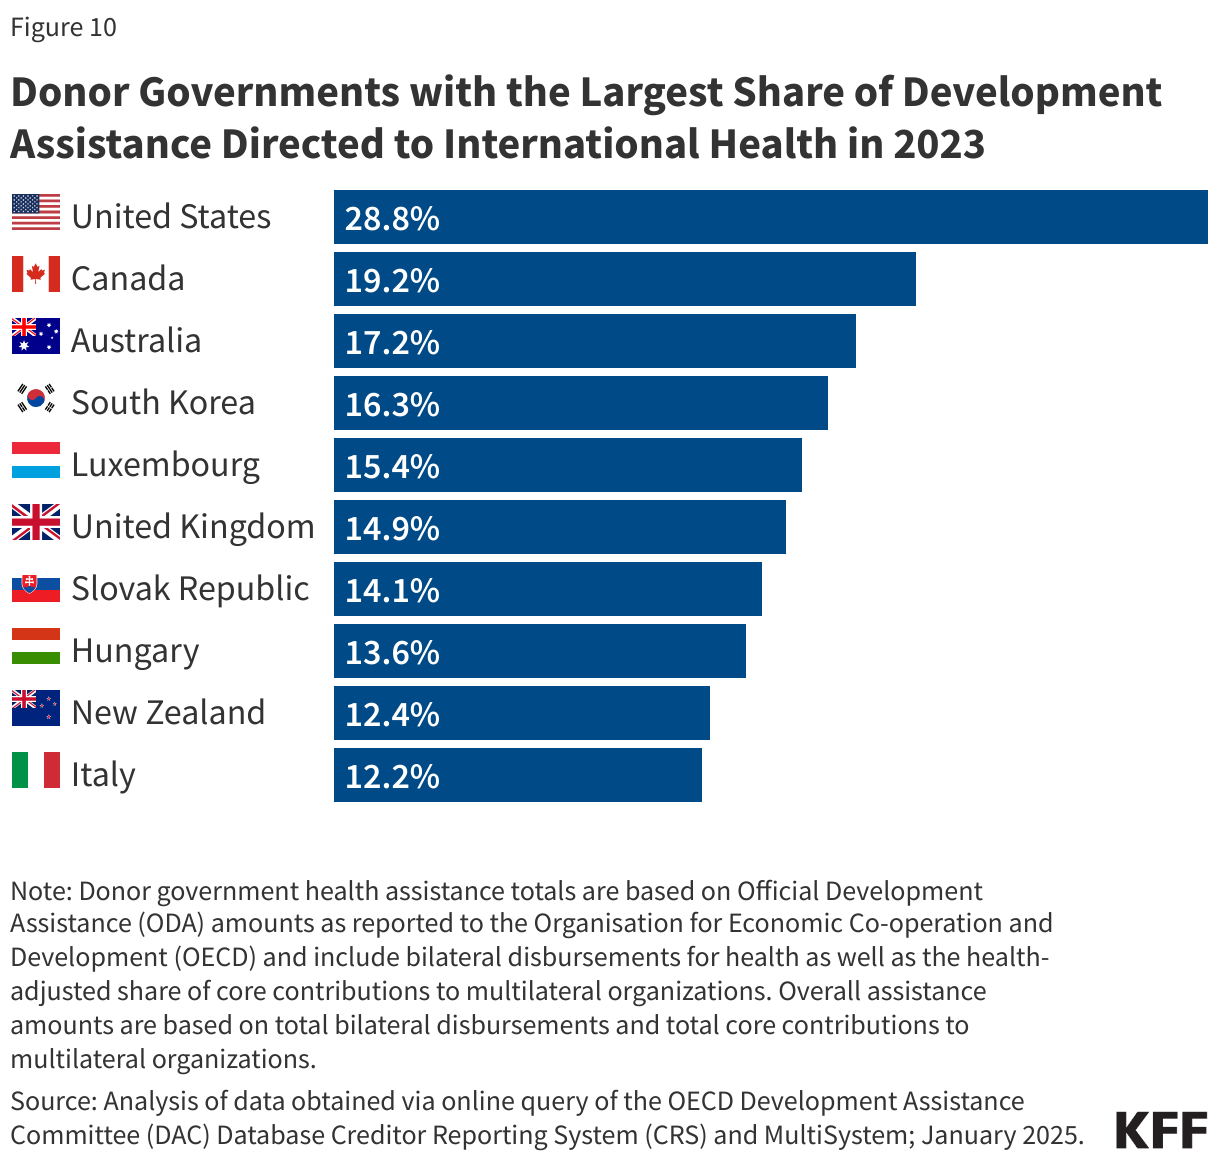
In addition, the U.S. has historically devoted more of its foreign assistance to health than any other donor government, contributing over a quarter of its foreign assistance to global health in 2023 (Figure 10). The U.S. has also been the largest government donor to several specific global health areas, including HIV and family planning. Currently, however, the Trump administration is withholding global health funds in several areas and actual spending levels are still unknown.

Donor Governments with the Largest Share of Development Assistance Directed to International Health in 2023

Future Outlook

Copy link to Future Outlook

While the U.S. has been engaged in international health activities for over a century and has historically been the largest funder and implementer of global health programs worldwide, it is currently undergoing a fundamental shift, with a significantly reduced footprint and role.  Given the prominence of the U.S. in global health, these actions have and will influence the larger global health ecosystem and the health of those in low and middle income countries. Among the key issues to watch are:

  • The future direction of U.S. leadership in and degree of commitment to global health as the Trump administration reorganizes foreign assistance more broadly and seeks to permanently alter the U.S. role.
  • The status of U.S. funding for global health, particularly given the interplay between Congress and the administration on whether and how that funding gets spent and ongoing litigation in this area.
  • The ability of global health implementers to continue to deliver services to those who need them, given their loss of funding and future uncertainty.
  • The future role of multilateral institutions in global health, as the U.S. bilateral role is reduced, but also its support for multilateral health efforts remains unclear.
  • Whether other donors (governments, foundations, the private sector) will help to fill some of the gaps left by the U.S.
  • Whether the nations that have been recipients of U.S. global health support will increase their own financing and delivery of health services to their populations.

Resources

Copy link to Resources

Citation

Copy link to Citation

Oum, S., Moss, K., & Kates, J., The U.S. Government and Global Health. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-the-u-s-government-and-global-health/ (date accessed).

LGBTQ+ Health Policy

Table of Contents

Introduction

Copy link to Introduction

The share of individuals identifying as LGBTQ+ in the United States has increased over time, rising from just 4% in 2012 to 8% in 2023. In addition, support for same-sex marriage has also grown (27% in 1996 v. 69% as of 2024) and fewer believe there should be less acceptance for LGBTQ+ people (26% in 2001 v. 8% in 2020). Increases in identity and acceptance have been punctuated by several Supreme Court decisions providing new civil rights for LGBTQ+ people. Still, widespread stigma and discrimination persist for many LGBTQ+ people, including in health care as well as across a range of social institutions. These experiences can fuel significant health care disparities among LGBTQ+ people, challenging well-being and affecting health outcomes. Further, LGBTQ+ rights and health care access have become increasingly politicized at the federal and state levels, especially when it comes to young people.

All people’s health and health care experiences are informed by the socioeconomic context in which they live, including the policy environment. Federal and state policy can facilitate or impede access to health care for LGBTQ+ people. At the federal level, there have been both expansions as well as restrictions in protections and access over time and across presidential administrations, including the second Trump administration. Starting on the first day of his second term, President Trump began to issue numerous executive actions, several of which directly address or affect health programs, efforts, or policies designed to meet the health needs of LGBTQ+ people. These include actions that seek to limit data collection, lessen civil rights protections, restrict access to care, and remove acknowledgement of diverse sexual and gender identities. At the state level, there has been a rapid increase in the number of laws and policies impacting LGBTQ+ people’s health, especially, though not exclusively, that of young people. An increasing number of legal challenges to federal and state laws may ultimately decide access to care and the extent to which protections remain. This chapter provides an overview of LGBTQ+ people’s identities, experiences with health and health care, and the related health policy landscape.

A Note on Language

Throughout this chapter, whenever possible, we use the term LGBTQ+ to represent the full spectrum of non-heterosexual, non-cisgender people. Additionally, people who are asexual, questioning, or intersex are sometimes included under the LGBTQ+ umbrella. However, at times, the reader may encounter differences in terminology (e.g., LGBT, LGB, etc.). In these circumstances, we use language to reflect the specific data being cited. It is important to note that the language used to describe LGBTQ+ people has evolved considerably over time and will likely continue to do so.

Sex, Sexual Orientation, and Gender Identity

Copy link to Sex, Sexual Orientation, and Gender Identity

The concepts of sex, gender, and sexual orientation are discreet. However, they are often thought of as interrelated and dependent on one another, though their actual relationship is more diverse and complex:

  • Sex is often described as one’s biological categorization of being male or female based on anatomical, hormonal, and genetic factors. At birth, individuals are typically assigned a sex based on external genitalia. While sex is often thought of as a binary, as many as 1.7% of the population has been estimated to have some intersex trait, with population estimates of people with anatomical variations being lower (less than 0.5% of the population).
  • Gender identity is an individual’s sense or experience of being male, female, transgender (trans), non-binary, gender non-conforming, or something else. Gender identity may or may not align with the sex that was assigned at birth. Gender expression is the public expression of gender identity, which may occur through attire, body characteristics (e.g., hair), voice, etc. Gender expression may or may not align with traditional assumptions related to sex or gender identity.
  • Sexual orientation refers to emotional, romantic or sexual attraction to other people, often in relationship to one’s own sex and/or gender identity.

While many people and institutions historically considered these three concepts to be inseparably linked and linear (e.g., assigned the male sex at birth, identifies as male, and is attracted to women), there is wide variation in how these concepts relate, and they can be dynamic over time.

Who Are LGBTQ+ People?

Copy link to Who Are LGBTQ+ People?

It is estimated that 9.3% of U.S. adults identify as LGBTQ+, as of 2024, nearly triple the share in 2012 (3.5%), and LGBTQ+ identity is expected to continue to increase over time. This increase may reflect changes in behavior and desire, and an increased willingness to self-identify and disclose as societal acceptance has grown. Indeed, these two factors are likely interrelated. LGBTQ+ identity is strongly associated with age; younger generations self-identify at higher rates than older generations (23% of those aged 18-27 identify as LGBTQ+ compared to just 2% among those aged 79 and older). In addition, as of 2023, about 1 in 4 high school students identifies as LGBQ+. As the LGBTQ+ population ages and new generations identify at higher rates, it is expected that the share of adults who identify as LGBTQ+ will increase as well.

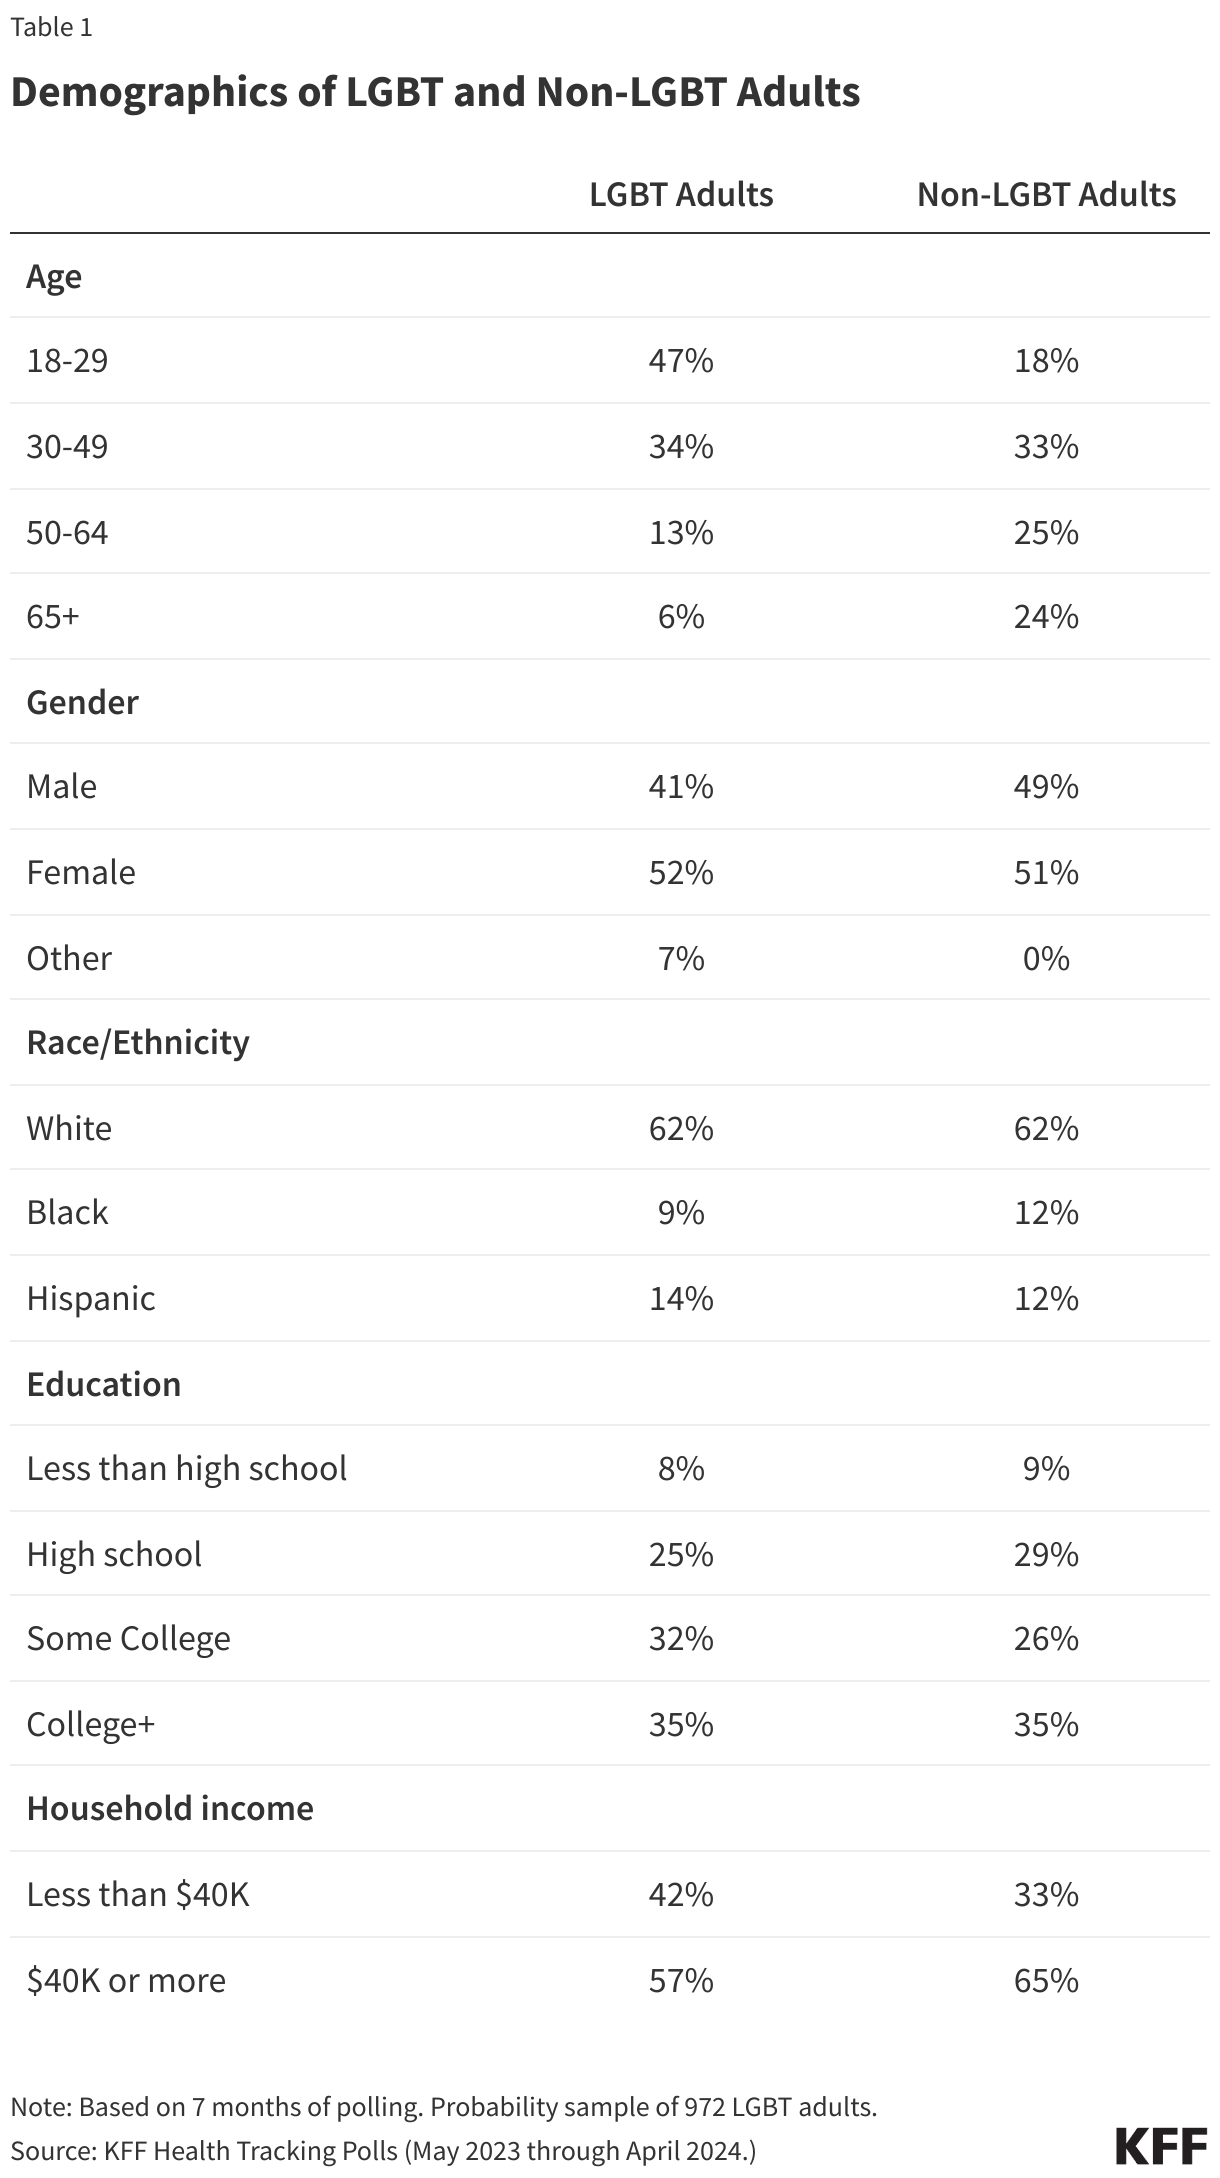
As such, the LGBTQ+ population is younger than the U.S. population overall. Almost half (47%) of LGBT adults are under age 30, compared to 18% of non-LGBT adults. Just 6% are 65 or older, compared to nearly one-quarter (24%) of non-LGBT adults (see Figure 1). LGBT adults are also more likely to have lower incomes and be living on less than $40,000 per year than non-LGBT adults (42% v. 33%), which may reflect their lower age. (See Table 1.)

Demographics of LGBT and Non-LGBT Adults

Within the LGBTQ+ community, identity is complex and multifaceted. Among adults who identify as LGBTQ+, the majority identify as bisexual (56%), a finding driven by younger adults, followed by gay (21%), and lesbian (15%). Smaller shares identify as transgender (14%), pansexual (1%), or in some other way (5%).

It is estimated that over 2.8 million adults and youth (over 13 years old) living in the U.S. identify as transgender or trans, which translates to 1% of all those 13 and older. A 2023 KFF/Washington Post Survey of a nationally representative sample of transgender adults in the U.S shows the trans adult population is younger than the larger cisgender adult population, with the majority of trans adults under the age of 35, echoing trends seen in the larger LGBTQ+ population. Additionally, most (70%) trans adults identify as lesbian, gay, or bisexual, compared to one in ten cisgender adults. Trans adults and cisgender adults do not notably differ when it comes to race and ethnicity or income. (See Table 2.)

A table shows demographic differences between transgender and cisgender adults. Transgender adults are younger than cisgender adults with just over half being 18-34 years old compared to just over a quarter of cisgender adults. They are also more likely to identify as lesbian, gay or bisexual (70% vs. 8%). There are not major differences between the groups by income or race/ethnicity.

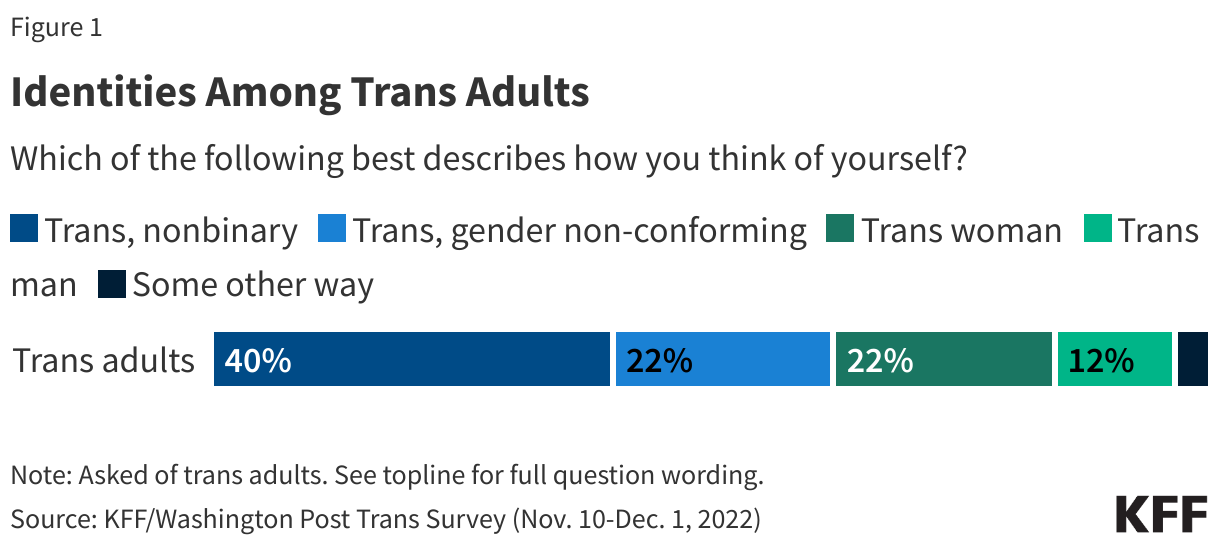
Most trans adults, or about 6 in 10, describe themselves as “trans, gender non-conforming” or “trans, nonbinary,” while smaller shares say they would describe themselves as a “trans woman” (22%) or a “trans man” (12%). (See Figure 1.)

Stacked horizontal bar chart shows responses from trans adults to the question, “Which of the following best describes how you think of yourself?” The largest share, 40%, identify as “Trans, nonbinary.” Another 22% identify as “Trans, gender non-conforming,” and 22% identify as a “Trans woman.” About 12% identify as a “Trans man.” A small remaining share identify “Some other way.”

In addition to sexual orientation and gender identity, the lives of people who are LGBTQ+ are also shaped and informed by a range of other intersectional sociodemographic factors, including race/ethnicity, income, geography, educational opportunities, language, citizenship status, disability status, and other variables, which, together, affect health access and outcomes in both positive and negative ways.

Data Collection

Having an understanding of who the LGBTQ+ community is, what challenges they face, what their health needs are, and how those differ from non-LGBTQ+ people allows policymakers, providers, and others to better meet the community’s needs. While the share of people who identify as LGBTQ+ has increased over time, the community is still a relatively small share of the overall population (approximately 8%). This makes representative data collection more difficult, particularly for sub-group analysis, since obtaining a representative sample of a small population requires a relatively larger sample size, which can be both challenging to obtain and costly. In addition to methodological challenges, in many cases, researchers, systems, and surveys simply haven’t asked about sexual orientation and gender identity. While the federal government had been moving towards greater data collection on sexual orientation and gender identity, some of that has been reversed in the second Trump administration and it is still not routine in state and local surveys, or in health systems, providers’ offices and employment, among other settings.

How data are collected is also important for reaching and understanding the needs and experiences of LGBTQ+ people. Best practice suggests data should be collected in ways that align with tested standards, conducted in culturally sensitive ways (accompanied by adequate training), secured responsibly, and then used to improve the lives of the people it represents. (See section on policy impact on LGBTQ+ people’s health.)

Stigma & Discrimination

Copy link to Stigma & Discrimination

Many LGBTQ+ people report having experienced stigma and discrimination in health care and other social institutions due to their actual or perceived sexual orientation, gender identity, and/or gender expression.

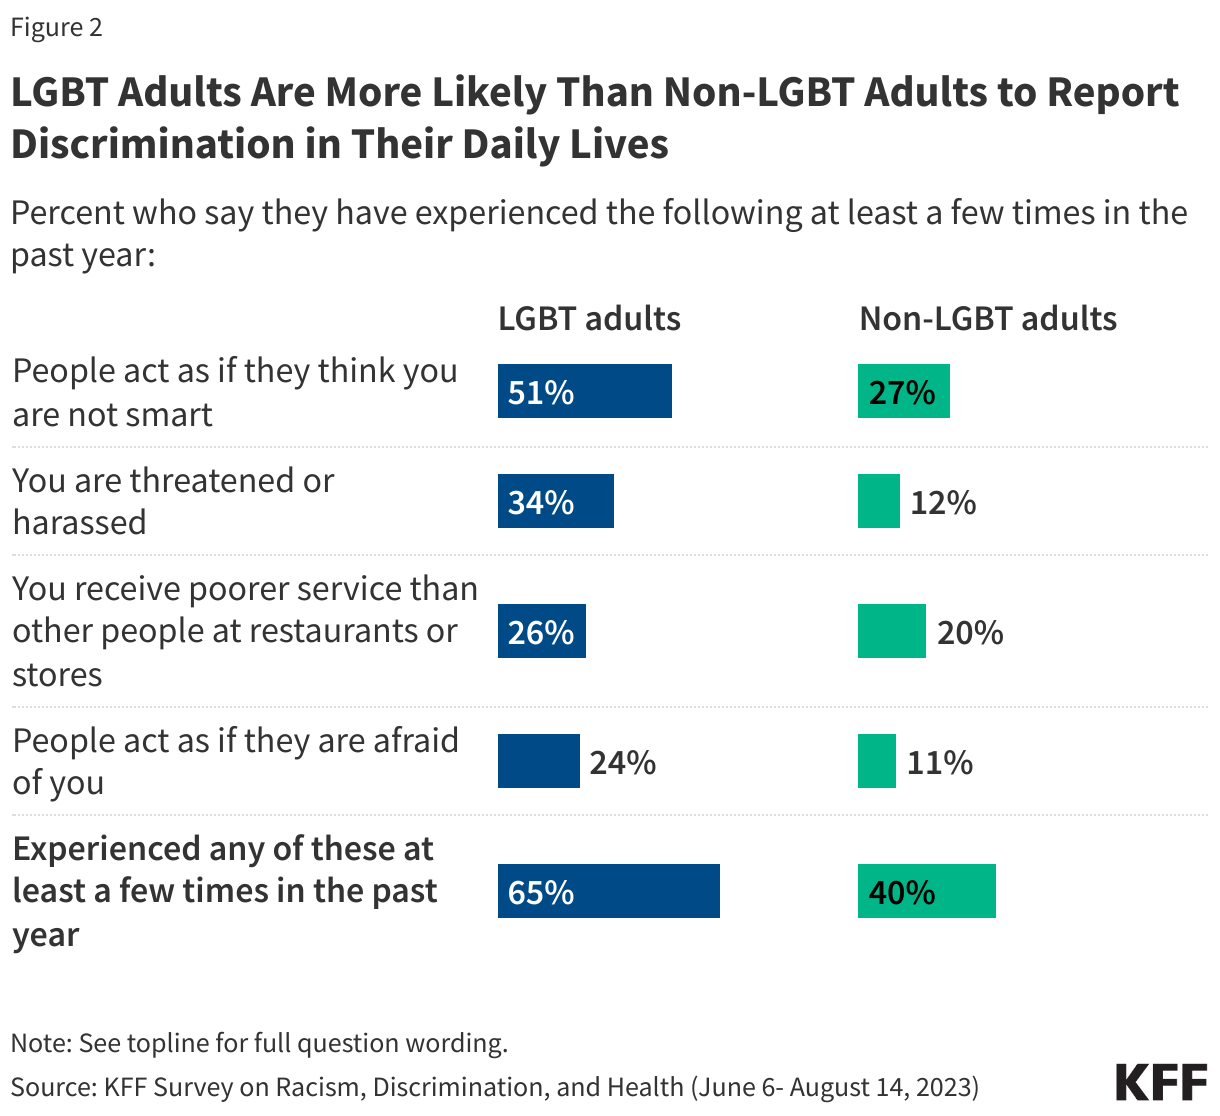
KFF polling has shown that LGBT adults face higher rates of discrimination and unfair treatment in their daily lives compared to others, with about two-thirds (65%) saying they have experienced at least one type of discrimination at least a few times in the past year, compared to four in ten non-LGBT adults. (See Figure 2.). These experiences are higher among LGBT adults who are younger and lower income.

Horizontal bar chart compares the share of LGBT adults and non-LGBT adults who report experiencing discrimination or mistreatment in daily life. About 65% of LGBT adults say they experienced at least one type of discrimination at least a few times in the past year, compared with about 40% of non-LGBT adults. The chart includes measures related to discrimination in daily interactions. Across the measures shown, LGBT adults consistently report higher rates of discrimination than non-LGBT adults. These include the following: people act as if they think you are not smart, you are threatened or harassed, you receive poorer service than other people at restaurants or stores, and people act as if they are afraid of you.

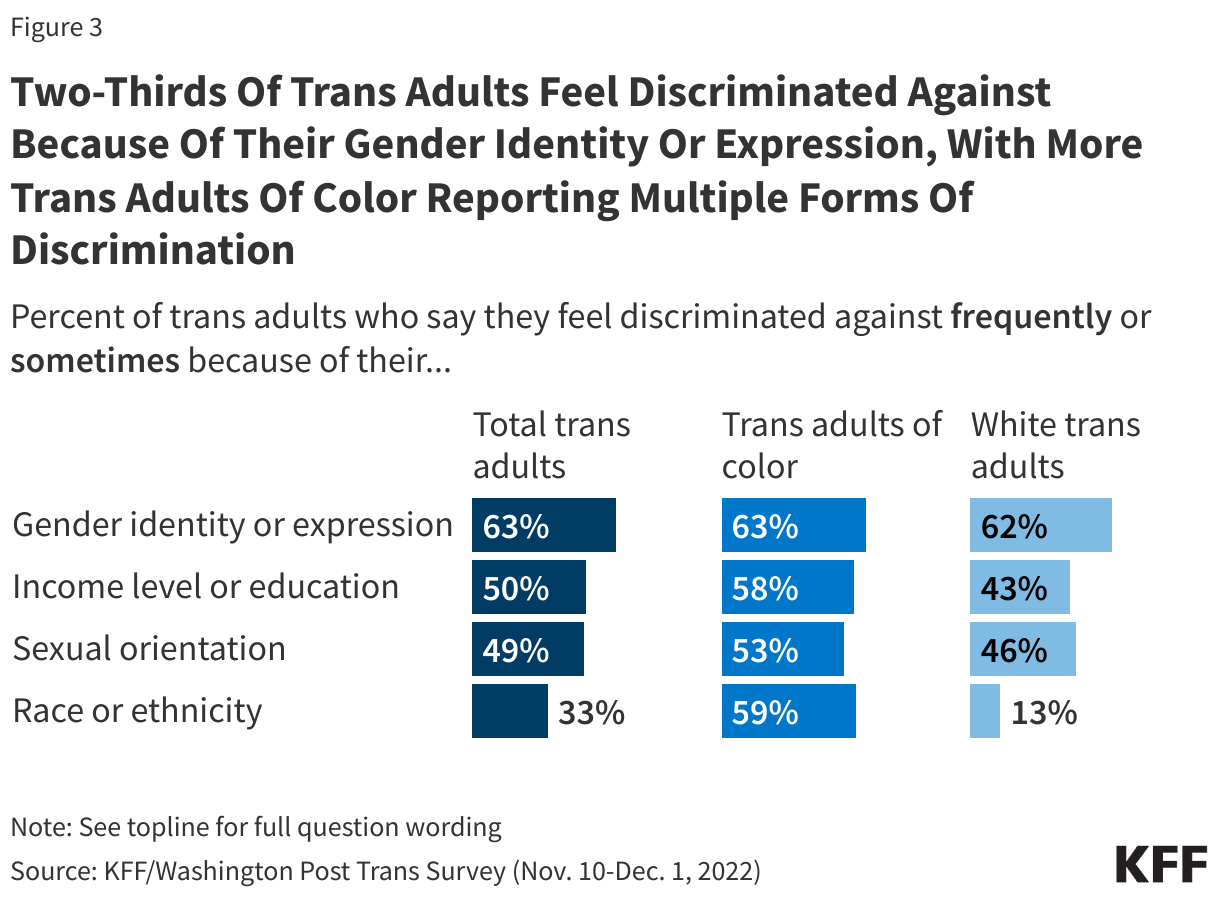
The KFF/Washington Post Trans survey found that many trans adults say they feel discriminated against at least “sometimes” due to their gender identity or expression, with trans adults of color even more likely to report multiple types of discrimination, including because of their race or ethnicity, income level or education, or sexual orientation, reflecting how discrimination can cut across intersecting identities. (See Figure 3.)

The figure consists of three groups of stacked bars representing trans adults overall, trans adults of color, and White trans adults. It shows the basis on which trans adults overall, trans adults of color, and White trans adults say they feel discriminated. These bases include gender identity/expression, income/education level, sexual orientation, and race/ethnicity. About two-thirds of trans adults say they experience discrimination related to their gender identity or expression, regardless of their race/ethnicity. The chart shows trans adults of color are more likely to report multiple types of discrimination, including because of their race or ethnicity, income level or education, or sexual orientation.

Experiences of stigma and discrimination also occur in health care settings, in part because pathologizing LGBTQ+ identity, behavior, and desire has a long history in medicine. Indeed, much of the early language of LGBTQ+ identity has its origins in 19th-century psychiatry, which defined LGBTQ+ people in opposition to heterosexual people (and health). The early medical literature promotedthe idea that individuals with LGBTQ+ behavior or desire needed treatment, a notion that persisted for more than a century in dominant medical literature and, in 1952, homosexuality was defined as a psychiatric disorder in the Diagnostic and Statistical Manual of Mental Disorders (DSM), the tool for classifying mental health conditions in the United States; it was not removed as such until 1974 (though as a compromise APA added “sexual orientation disturbance” as diagnosis which was then replaced with “ego dystonic homosexuality” which was not removed until 1987.) While mainstream medicine has evolved from the view of needing to treat LGBTQ+ identity as a medical or psychological disorder, stigma and discrimination within medicine persist.

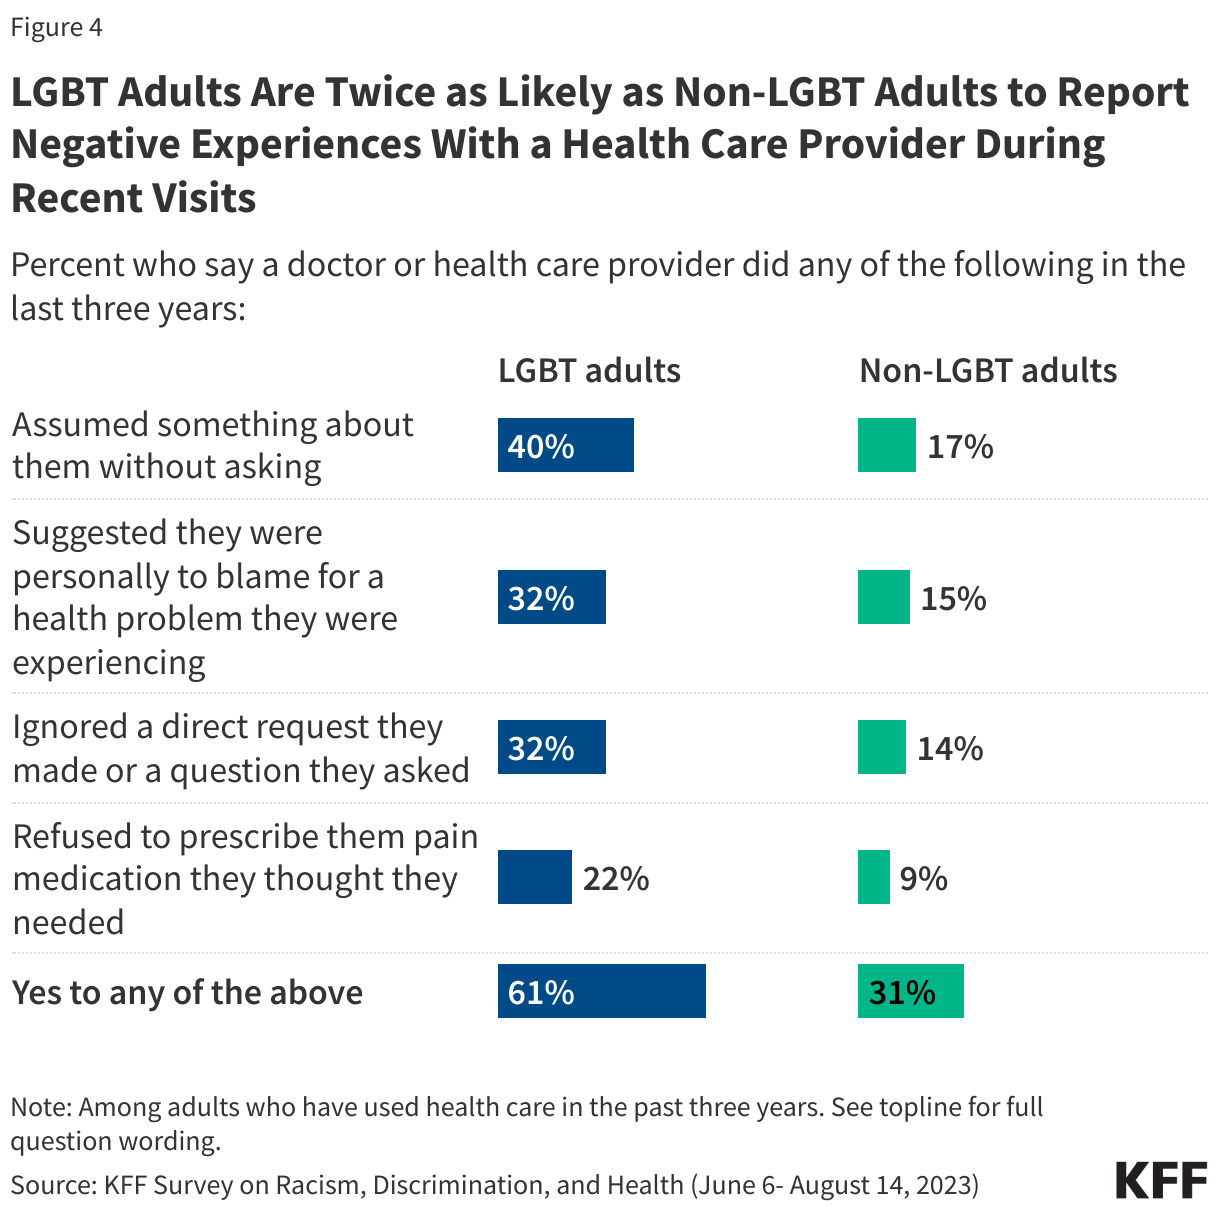
KFF polling shows that 6 in 10 LGBT adults report at least one of several negative experiences with a health care provider in the past three years – about twice the share of non-LGBT adults who report this. (See Figure 4.)

Horizontal bar chart titled, “LGBT Adults Are Twice as Likely as Non-LGBT Adults to Report Negative Experiences With a Health Care Provider During Recent Visits”,  compares the share of LGBT adults and non-LGBT adults who report experiencing discrimination or unfair treatment from a health care provider. LGBT adults are substantially more likely than non-LGBT adults to report negative experiences in health care settings, including having a provider assume something without asking, being blamed for a health problem, being ignored, or being refused pain medication. 61% of LGBT adults reported at least one of those challenges, compared to 31% non-LGBT adults.

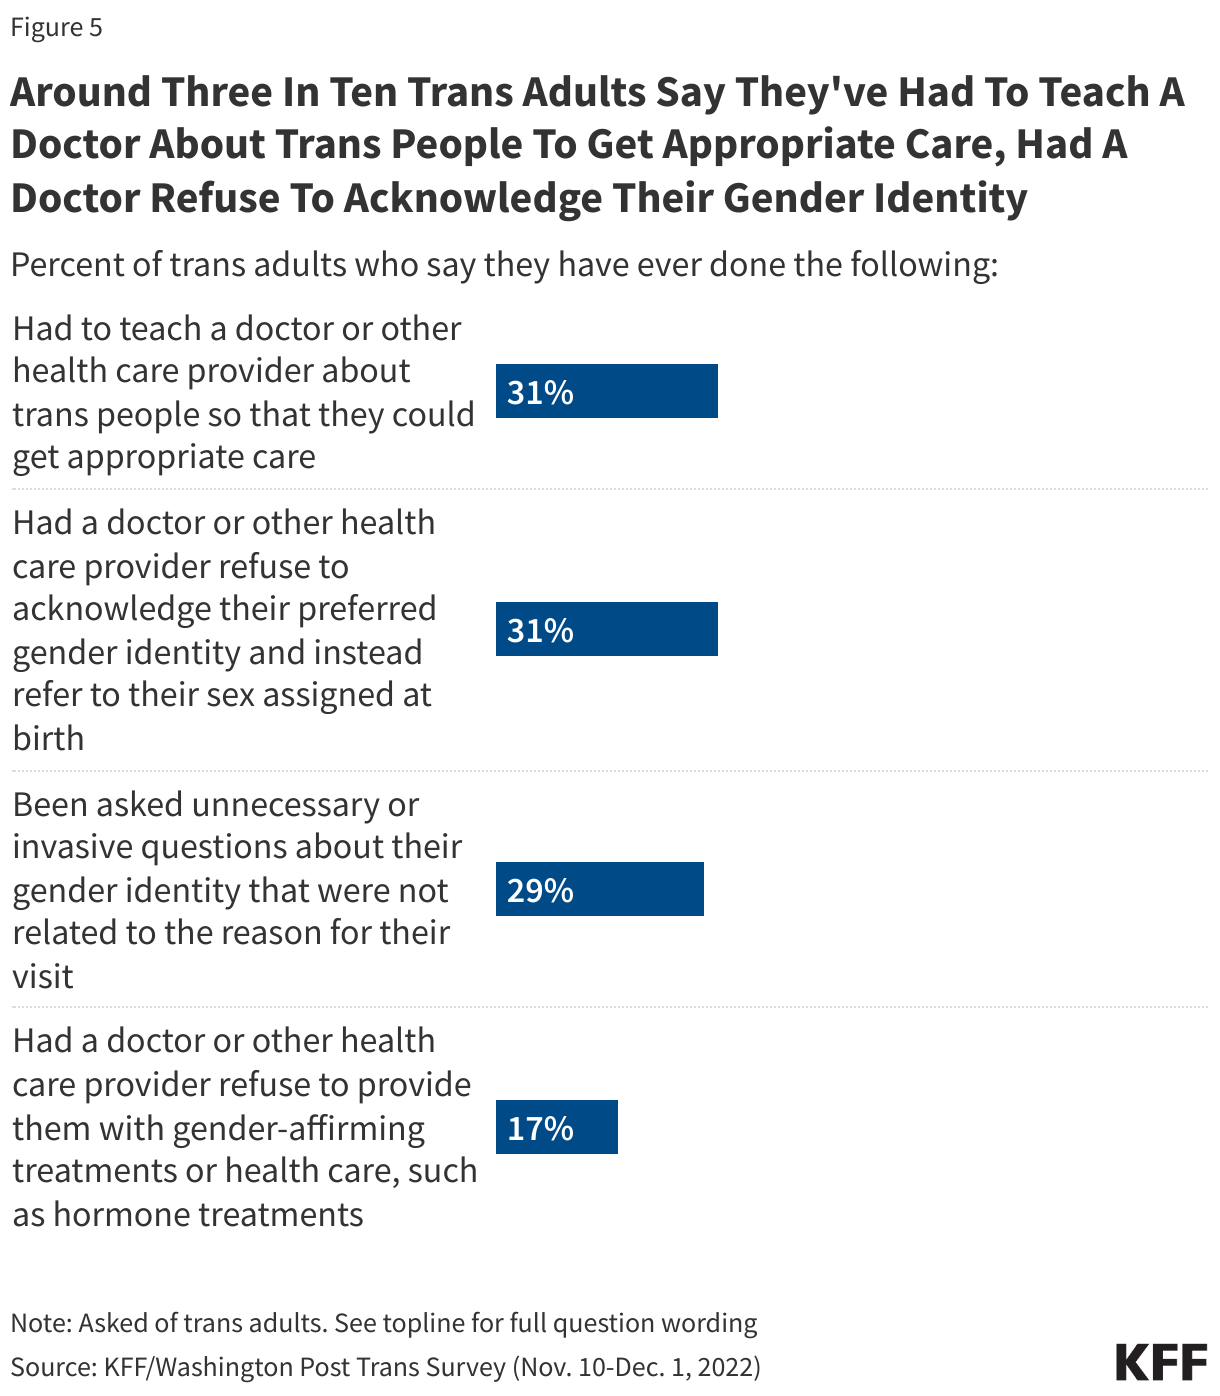
Additionally, about 3 in 10 trans adults say they have had to teach a doctor or other health care provider about trans people to receive appropriate care, had a doctor refuse to acknowledge their preferred gender identity, or been asked unnecessary or invasive questions about their gender identity that were unrelated to their care. (See Figure 5.)

Horizontal bar chart shows the share of trans adults reporting negative experiences in health care settings related to their gender identity. About three in ten trans adults say they had to teach a doctor or other health care provider about trans people in order to receive appropriate care. Similar shares say a provider refused to acknowledge their gender identity and separately asked unnecessary or invasive questions about their gender identity that were unrelated to the reason for their visit. 17% were denied gender affirming care.

Experiences of stigma, discrimination, and mistreatment based on sexual orientation or gender identity occur in multiple non-health care environments and institutions as well, and these also negatively affect health and well-being.

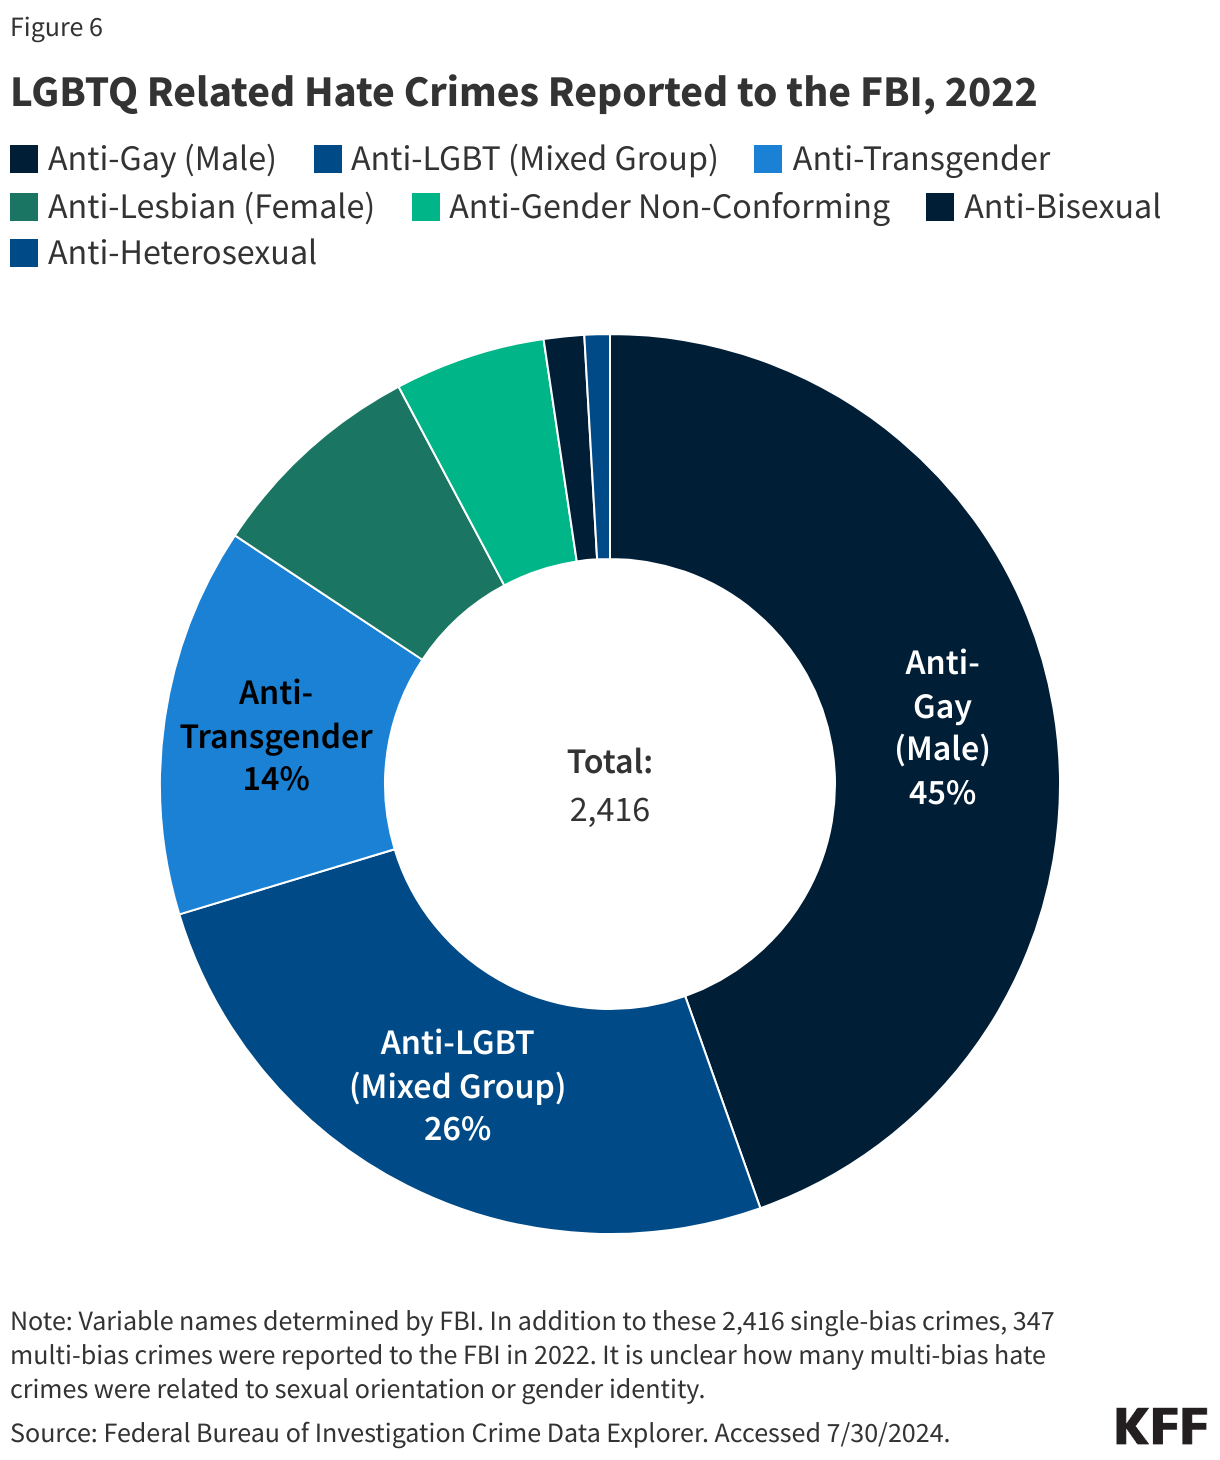
Hate crimes, defined as “bias against people or groups with specific characteristics that are defined by the law,” have negative effects on health, including both physical and psychological harm, and LGBTQ+ people are more likely to experience hate crimes than non-LGTBQ+ people. According to the FBI, in 2023, more than 1 in 5 hate crimes (23%) were related to being LGBTQ+. In 2022, of crimes related to being LGBTQ+, 17% were based on sexual orientation and 4% on gender identity, accounting together for 2,416 crimes in total. Hate crimes against gay men accounted for nearly half (45%) of these, followed by crimes against a combined group of LGBT people (26%), and then transgender people (14%). A smaller share was reported against lesbians (8%), gender non-conforming people (5%), bisexual people (1%), and heterosexual people (1%). (Notably, whether a hate crime gets reported to the FBI and how it is defined are highly variable, so these statistics are likely an underrepresentation of actual crimes that occur.) (See Figure 6.) LGBT+ people are also nine times more likely to self-report that they have experienced a hate crime than non-LGBT+ people.

LGBTQ Related Hate Crimes Reported to the FBI, 2022

Sexual violence, in particular, is a common experience among LGBTQ+ people relative to non-LGBTQ+ people and is especially high among bisexual women and gay and bisexual men. Bisexual women report higher lifetime experiences with rape, other sexual violence and stalking, and lesbian women report higher rates of sexual violence and unwanted sexual contact across their lifetimes than heterosexual women. Gay and bisexual men report higher rates of sexual violence, unwanted sexual experiences, and sexual coercion than heterosexual men, with gay men also reporting higher rates of stalking across their lifetimes than heterosexual men.

Transgender people also face higher rates of intimate partner violence and are more likely to be the victim of a violent crime, with surveys finding that trans people report high rates of violence across a range of measures. KFF polling shows that a majority of trans adults (64%) say they have been verbally attacked and 1 in 4 say they have been physically attacked because of their gender identity, gender expression, or sexual identity. The share of trans adults who have been physically attacked because of their gender identity increases to 31% among trans people of color.

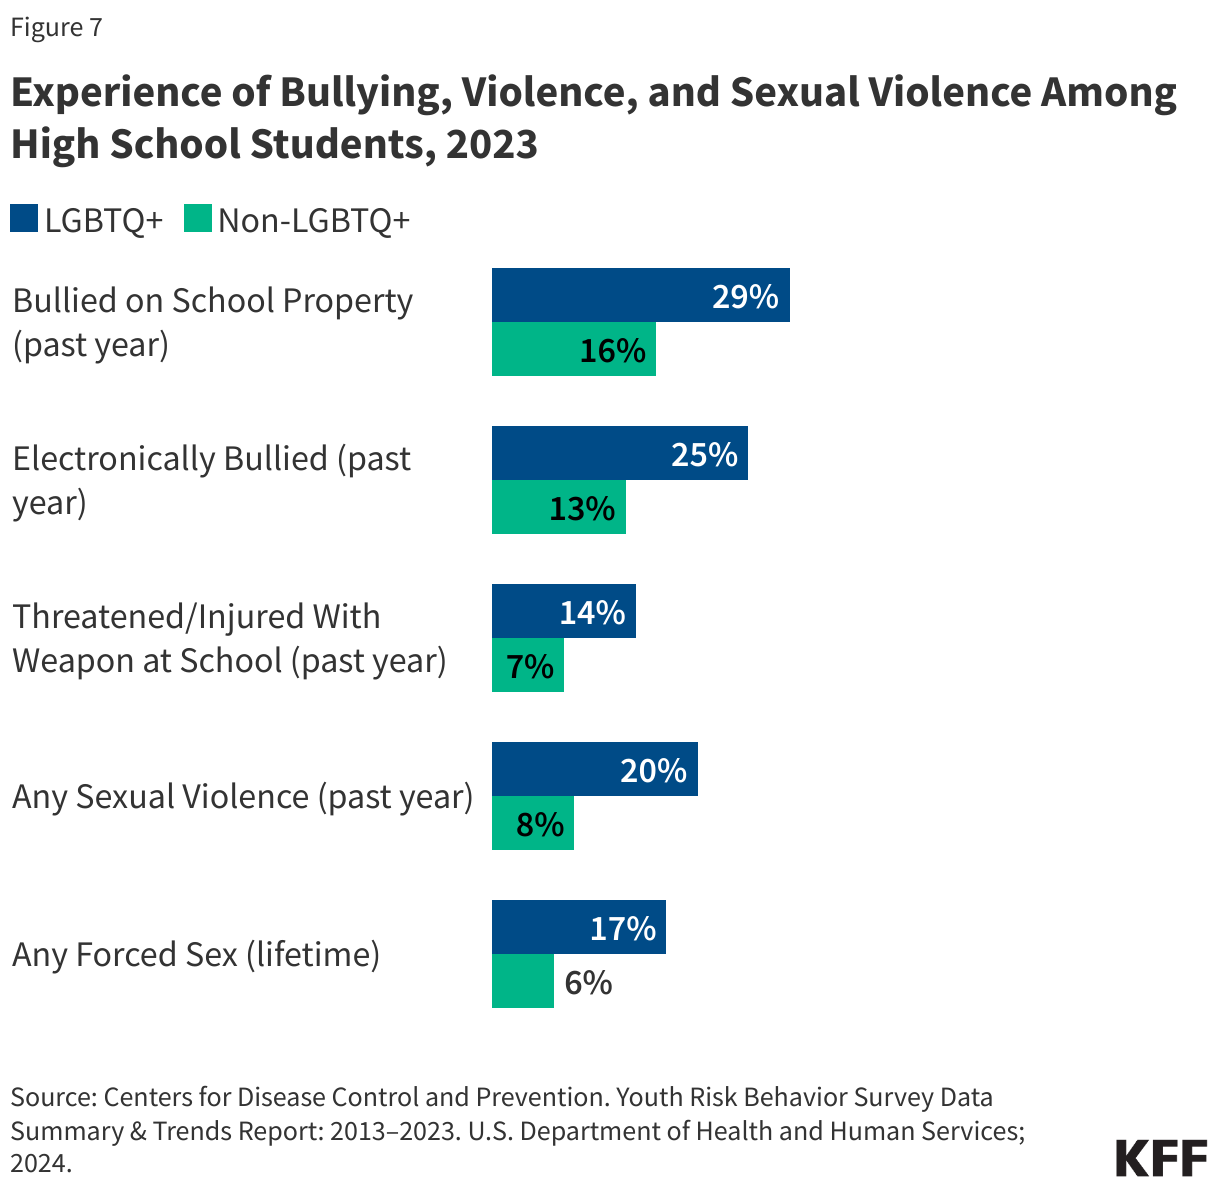
Young LGBTQ+ people are also impacted by higher rates of bullying and violence, including sexual violence, compared to non-LGBTQ+. LGBTQ+ high school students report higher rates of being bullied than non-LGBTQ+ students, with LGBTQ+ students about twice as likely as non-LGBTQ+ students to report that they have been bullied on school property (29% v. 16%) or to report electronic bullying (25% v. 13%). Additionally, LGBTQ+ high school students are twice as likely to report having been injured or threatened with a weapon at school compared to non-LGBTQ+ students (14% v. 7%). Experiences with sexual violence generally (20% v. 8%) and forced sex in particular (17% v. 6%) were also more common among LGBTQ+ high school students than non-LGBTQ+ high school students. (See Figure 7.)

The grouped bar chart compares LGBTQ+ and non-LGBTQ+ high school students experiences related to bullying and violence in 2023. LGBTQ+ students report higher rates than non-LGBTQ+ students across all categories shown: being bullied on school property (29% vs. 16%), electronic bullying (25% vs. 13%), being injured or threatened with a weapon at school (14% vs. 7%), experiencing sexual violence (20% vs. 8%), and experiencing forced sex (17% vs. 6%).

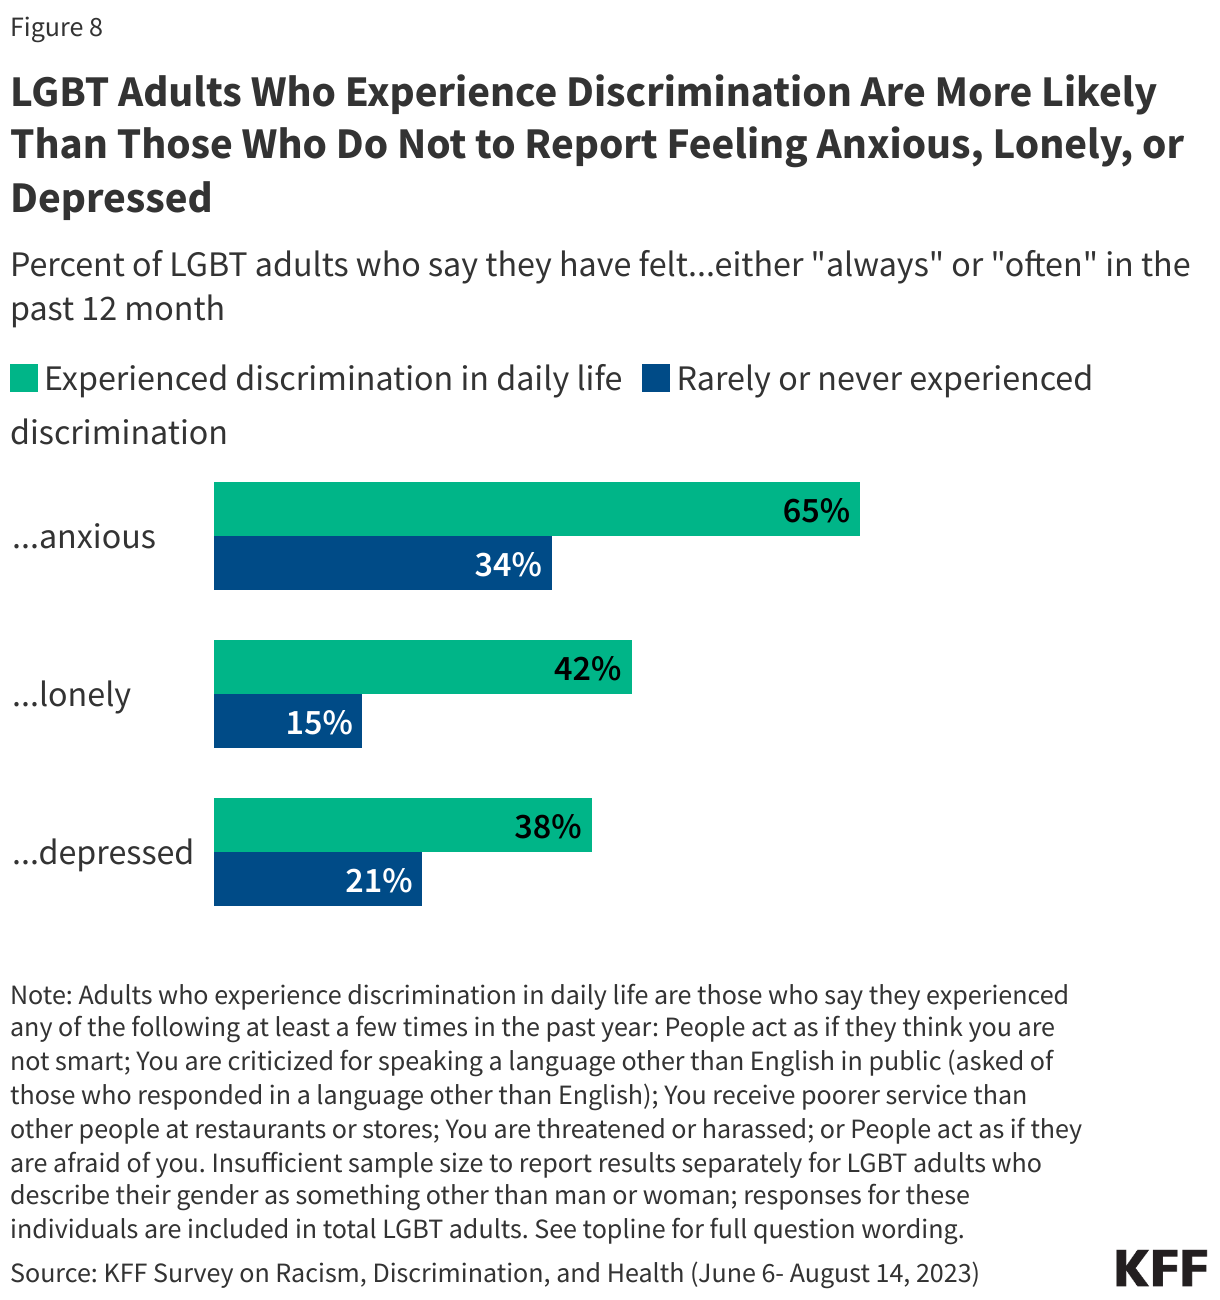
LGBTQ+ people’s disproportionate experiences of maltreatment, stigma, and discrimination can have a significant and negative impact on present and future mental health. Indeed, LGBT adults who had recent experiences with at least one form of discrimination in the past year are more likely to report feeling always or often lonely (42% v. 15%), depressed (38% v. 21%) or anxious (65% v. 34%) than those who rarely or never experienced discrimination in daily life. Additionally, larger shares of LGBT women, younger LGBT adults, and lower-income LGBT adults report regular feelings of anxiety, loneliness, or depression. While other underlying factors beyond discrimination may contribute to these differences, the relationship between feelings of loneliness, anxiety, and depression and experiences with discrimination among LGBT adults remains significant even after controlling for race/ ethnicity, education, income, gender, and age (see section on mental health below). (See Figure 8.)

The grouped bar chart shows differences in experiences of ongoing anxiety, loneliness, and depression among LGBT adults, looking at these experiences among LGBT adults who experienced discrimination in the past year and those who did not. Among those who experienced discrimination, 65% of LGBT adults report feeling anxious always or often anxious, compared with 34% among those who did not. Thirty-eight percent of LGBT adults experiencing discrimination report feeling always or often depressed, compared with 21% among those who did not. Forty-two percent of LGBT adults experiencing discrimination report feeling always or often lonely, compared with 15% among those who did not.

Health Coverage and Access

Copy link to Health Coverage and Access

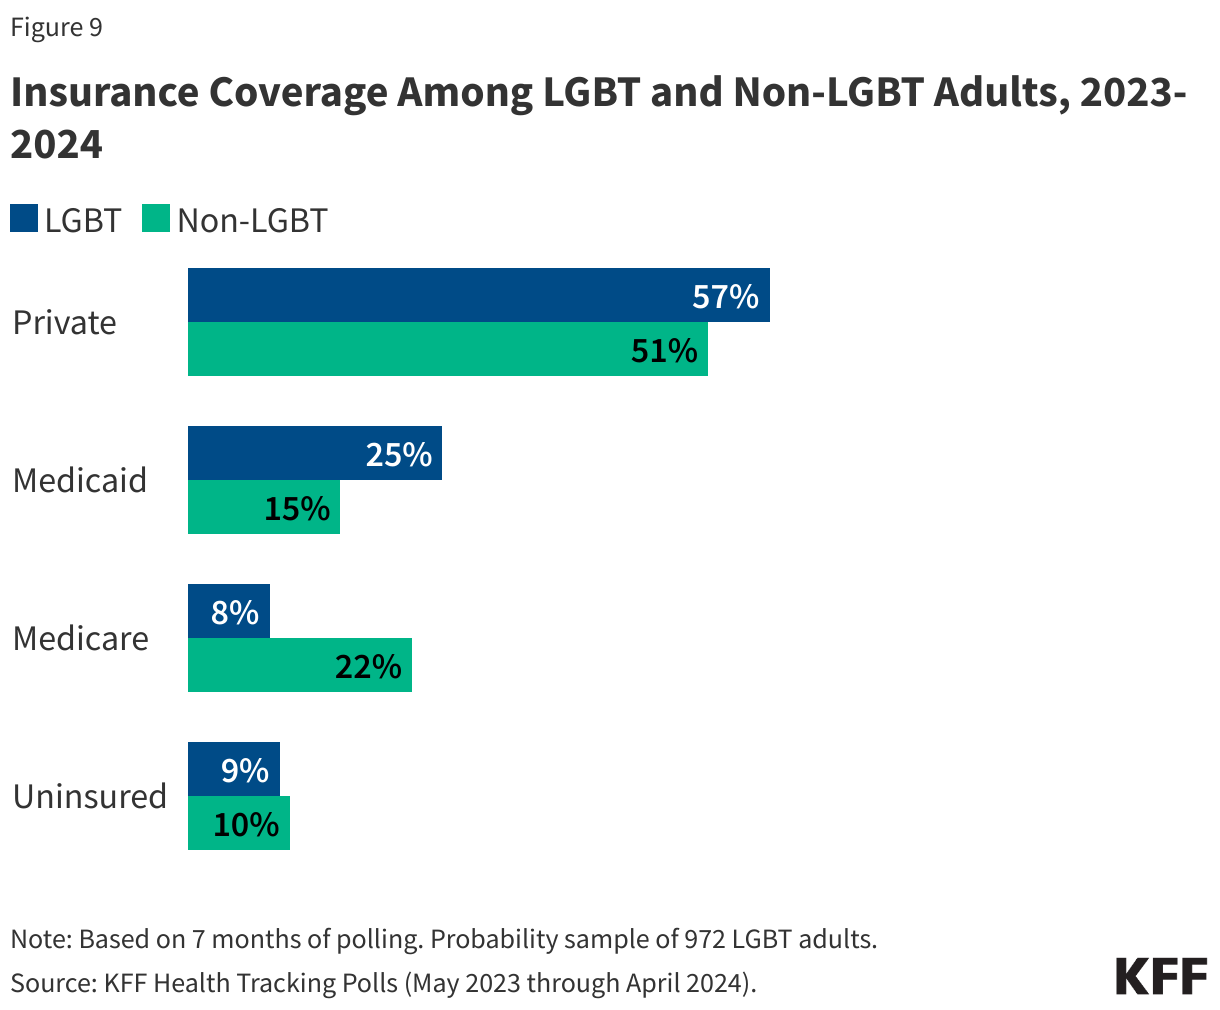
Overall, LGBT people report similar rates of being uninsured as non-LGBT people (9% v. 10%). LGBT adults, who are notably both younger and lower income than the general population, have higher rates of Medicaid coverage (25% v. 15%) and lower rates of Medicare coverage (8% v. 22%). They are slightly more likely to be covered by private insurance than non-LGBT adults (57% v. 51%). (See Figure 9.)

The grouped bar chart compares health insurance coverage among LGBT adults and non-LGBT adults. Both groups report similar rates of being uninsured (9% for LGBT adults vs. 10% for non-LGBT adults). LGBT adults are more likely to have Medicaid coverage (25% vs. 15%) and slightly more likely to have private insurance (57% vs. 51%). In contrast, LGBT adults are less likely to have Medicare coverage (8% vs. 22%) compared to non-LGB+ adults.

Research has found that having a usual source of care is associated with increased use of preventive care and better health outcomes, but LGBT people are more likely to report not having a usual source of care than non-LGBT people (19% v. 12%). (From KFF’s Survey of Racism, Discrimination, and Health). One study found that LGBTQ people were more likely to lack access to providers, delay care, face issues taking medications due to cost, and have fewer routine checkups than heterosexual cisgender people.

KFF polling has also found that many LGBT adults say negative health care experiences have affected their willingness to seek care, their health care coverage, and their physical health. For example, LGBT adults are significantly more likely than non-LGBT adults to report that having a negative health care experience in the last three years caused their health to get worse (24% v. 9%), made them less likely to seek health care (39% v. 15%), or caused them to switch health care providers (36% v. 16%).

LGBTQ+ People's Health Today

Copy link to LGBTQ+ People's Health Today

While in some areas, the health experiences of LGBTQ+ people mirror those of non-LGBTQ+ people, in other areas, LGBTQ+ people face disparities in health outcomes due to their sexual orientation and gender identity, as well as other factors such as race/ethnicity, class, nationality, and age. Disparities related to mental health, substance use, and sexual health are especially apparent, and LGBTQ+ people also experience certain chronic conditions at higher rates than heterosexual and cisgender people. In some cases, these are driven by social factors such as the biosocial impact of experiencing stigma and discrimination, higher rates of alcohol use and smoking, and obesity. They may also stem from fear of engaging with the health system, including from past experiences of discrimination, which may lead to forgoing routine screening or needed care.

There may also be a link between health care access, competency, and affordability (discussed above) and the ability to detect, control and treat disease. For example, research has found that transgender and gender-diverse people are both less likely to receive cancer screenings and also have a higher incidence of HIV- and HPV-associated cancers.

Overall Health Status

Despite being a younger population, a group traditionally reporting higher levels of well-being, LGBT people are more likely to report being in fair or poor physical health than non-LGBT people (26% v. 19%).

LGBT+ people also report that they are managing chronic conditions and living with disabilities that impact daily life at higher rates than non-LGBT+ people. Half (50%) of LGBT+ people reported that they had an ongoing health condition that requires regular monitoring, medical care, or medication, compared with 45% of non-LGBT+ people. Additionally, one-quarter (25%) of LGBT+ people reported having a disability or chronic disease that keeps them from participating fully in work, school, housework, or other activities, compared with 16% of non-LGBT+ people.

Likewise, a larger share of LGBT+ people report taking at least one prescription medication on a regular basis than non-LGBT+ people (62% v. 55%). This includes more than half (54%) of young LGBT+ adults (ages 18 to 24) who reported regularly taking a prescription compared to just over one-third (36%) of non-LGBT+ adults in the same age group.

Chronic Conditions

Studies have found disparities in certain chronic conditions among LGBTQ+ people, including reports of higher rates of diabetes among lesbians and gay and bisexual men and higher rates of cardiovascular diseases and cancers in certain populations. One study found LGBTQ+ survey respondents were more likely to report having asthma, arthritis, diabetes, kidney disease, hypertension, cardiovascular disease, heart attack, stroke, and chronic obstructive pulmonary disease (COPD) than non LGBTQ+ respondents.

HIV and STIs

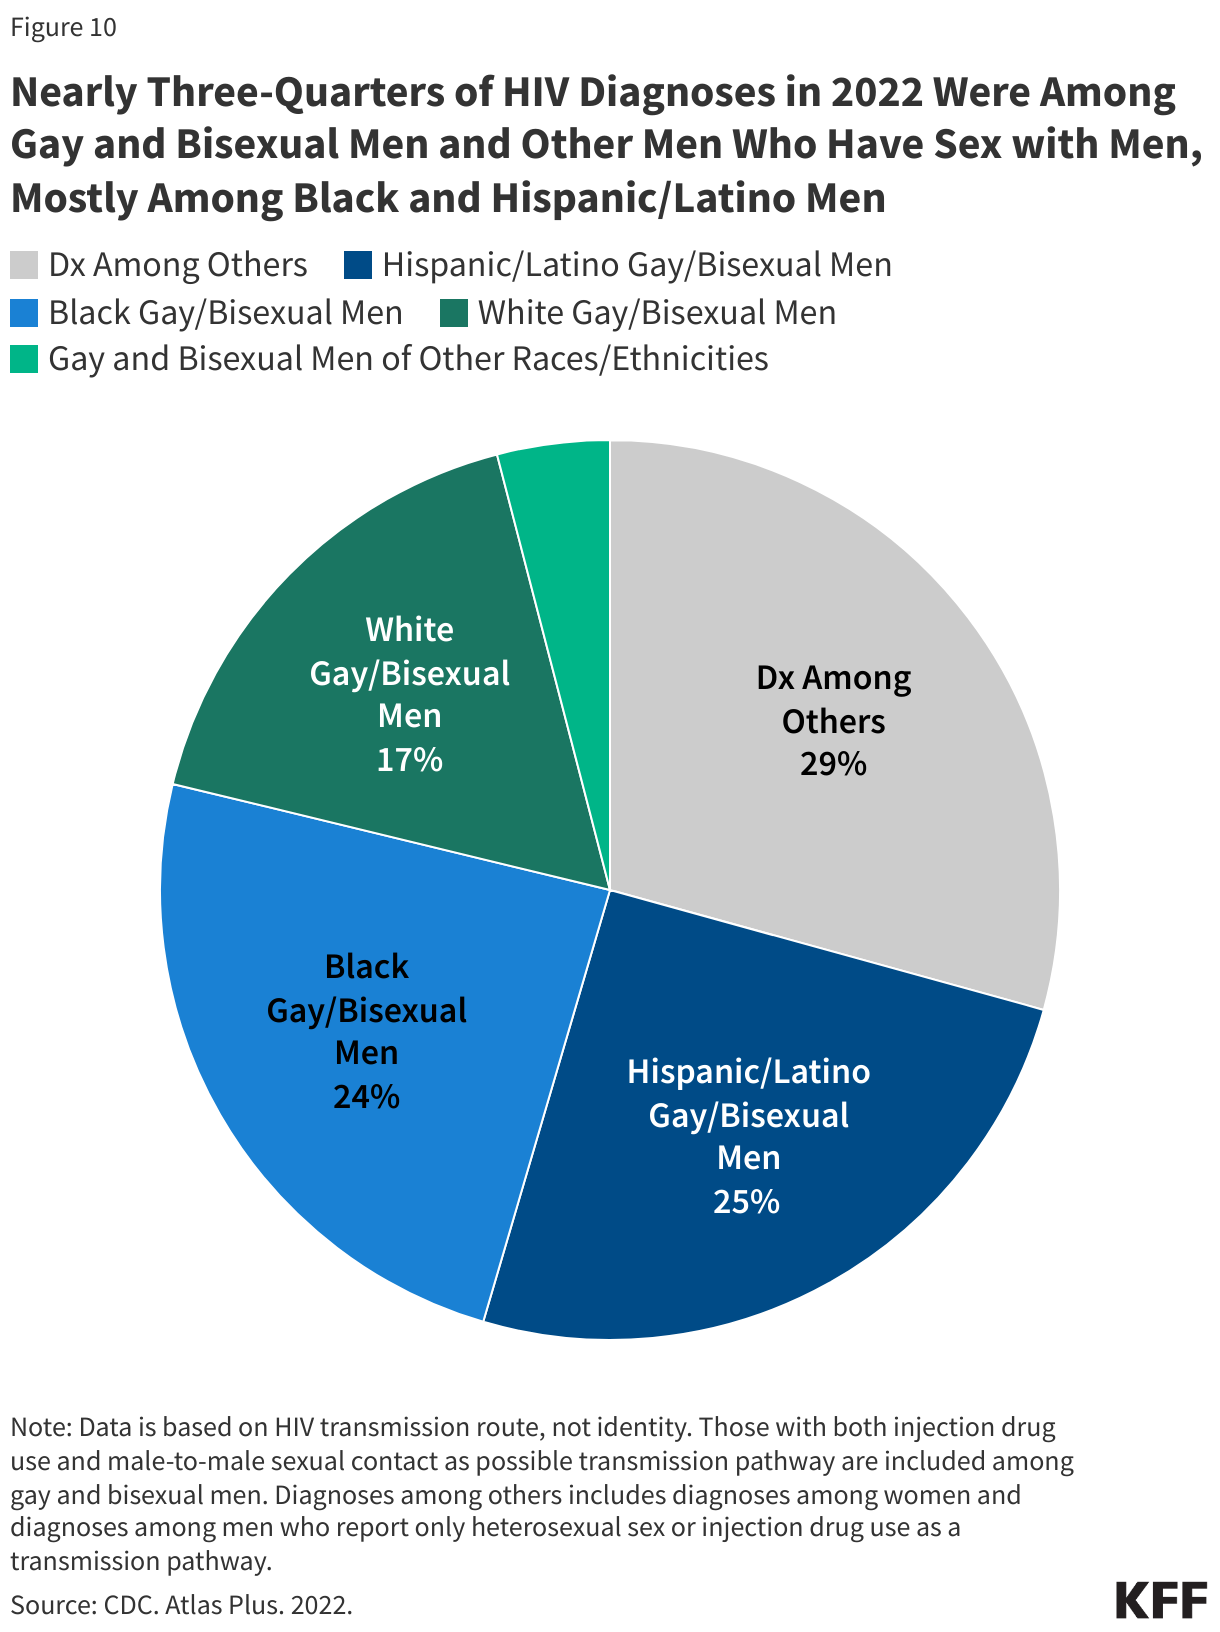
There are significant HIV and STI-related disparities among gay and bisexual men, other men who have sex with men, and transgender women compared to other groups and the population as a whole. These disparities may arise for a range of reasons, including sexual networks, differences in behavior, and biological or social factors. In addition, increased incidence of HIV and STIs can, in turn, put these groups at higher risk for other comorbid conditions like other STIs and certain cancers. Nearly three-quarters (71%) of people diagnosed with HIV in 2022 were gay and bisexual men or other men who have sex with men, and of those, young Black and Latino men were disproportionately represented. (See Figure 10.)

Nearly Three-Quarters of HIV Diagnoses in 2022 Were Among Gay and Bisexual Men and Other Men Who Have Sex with Men, Most Were Among Black and Hispanic Men

A meta-analysis estimated that 14% of transgender women and 3% of transgender men are HIV positive. Black and Hispanic transgender women are disproportionately impacted, with prevalence estimates of 44% and 26%, respectively.

Among those seeking care at STD clinics, gay and bisexual men are more likely to test positive for gonorrhea and chlamydia than women or heterosexual men. An estimated 58% of cases of primary and secondary syphilis reported among men with known sex of sex partners in 2023 were among gay and bisexual men and other men who have sex with men, and cases have increased significantly over the past decade. Additionally, the 2022 mpox outbreak occurred almost exclusively among gay and bisexual men and other men who have sex with men, with Black and Hispanic men being especially impacted. While data are limited on gender identity and STIs, studies have indicated that incidence and prevalence levels of gonorrhea and chlamydia among transgender women are similar to those among cisgender gay and bisexual men.

Mental Health and Substance Use

LGBTQ+ people face greater mental health challenges and disparities than non-LGBTQ+ people, including in accessing mental health care. The drivers of these disparities are complex and may relate, in part, to widespread experiences of stigma and discrimination (as described above). Current attempts to institute anti-LGBTQ+ policies in many states and communities may contribute to poor mental health outcomes and increase the need for care.

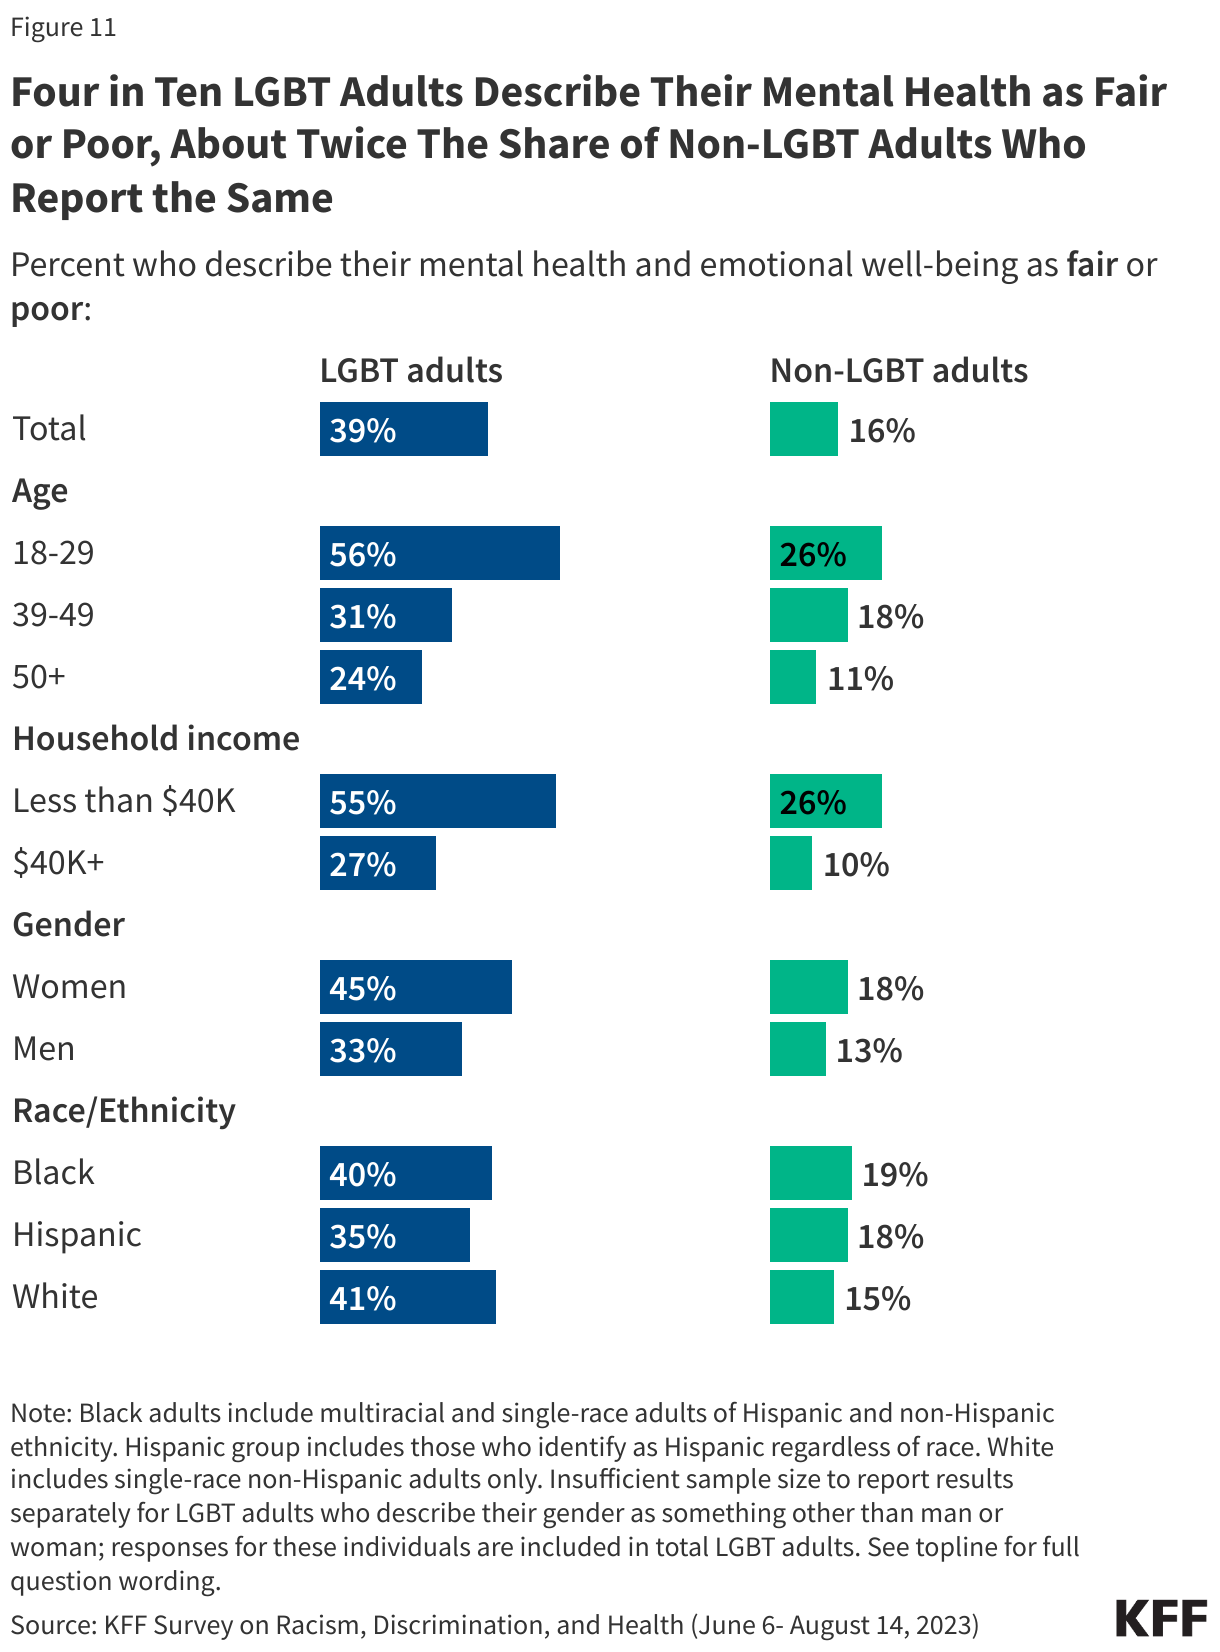
LGBT adults are more likely than non-LGBT adults to describe their mental health and emotional well-being as either “fair” or “poor” (39% v. 16%). LGBT adults with household incomes below $40,000 are about twice as likely as LGBT adults with higher incomes to report fair or poor mental health (55% v. 27%), as are LGBT adults ages 18-29 compared to those ages 50 and older (56% v. 24%). Across racial and ethnic groups, about 4 in 10 Black (40%), Hispanic (35%) and White (41%) LGBT adults describe their mental health as fair or poor. (See Figure 11.)

The figure shows two columns of bar charts comparing self-reported mental health status between LGBT adults and non-LGBT adults, by different demographic variables. OverallOverall, it show 39% of LGBT adults describe their mental health as fair or poor, compared with 16% of non-LGBT adults. LGBT adults who are younger or lower income are most likely to report poor or fair mental health.  Differences are smaller by gender and similar across race/ethnicities.

More specifically, about half (54%) of LGBT adults report feeling anxious either “always” or “often” in the past year, while a third report feeling lonely (33%) or depressed (32%) “always” or “often” – more than twice the shares of non-LGBT adults who report the same. As noted earlier, those who experienced recent discrimination were more likely to report these feelings than those who did not. 

LGB adults also report having serious thoughts of suicide, making a suicide plan, or attempting suicide at higher rates than non-LGB adults, with disparities especially pronounced among bisexual adults. LGB adults also report higher rates of substance use and substance use disorder (SUD) than non-LGB adults, with rates especially high among bisexual adults.

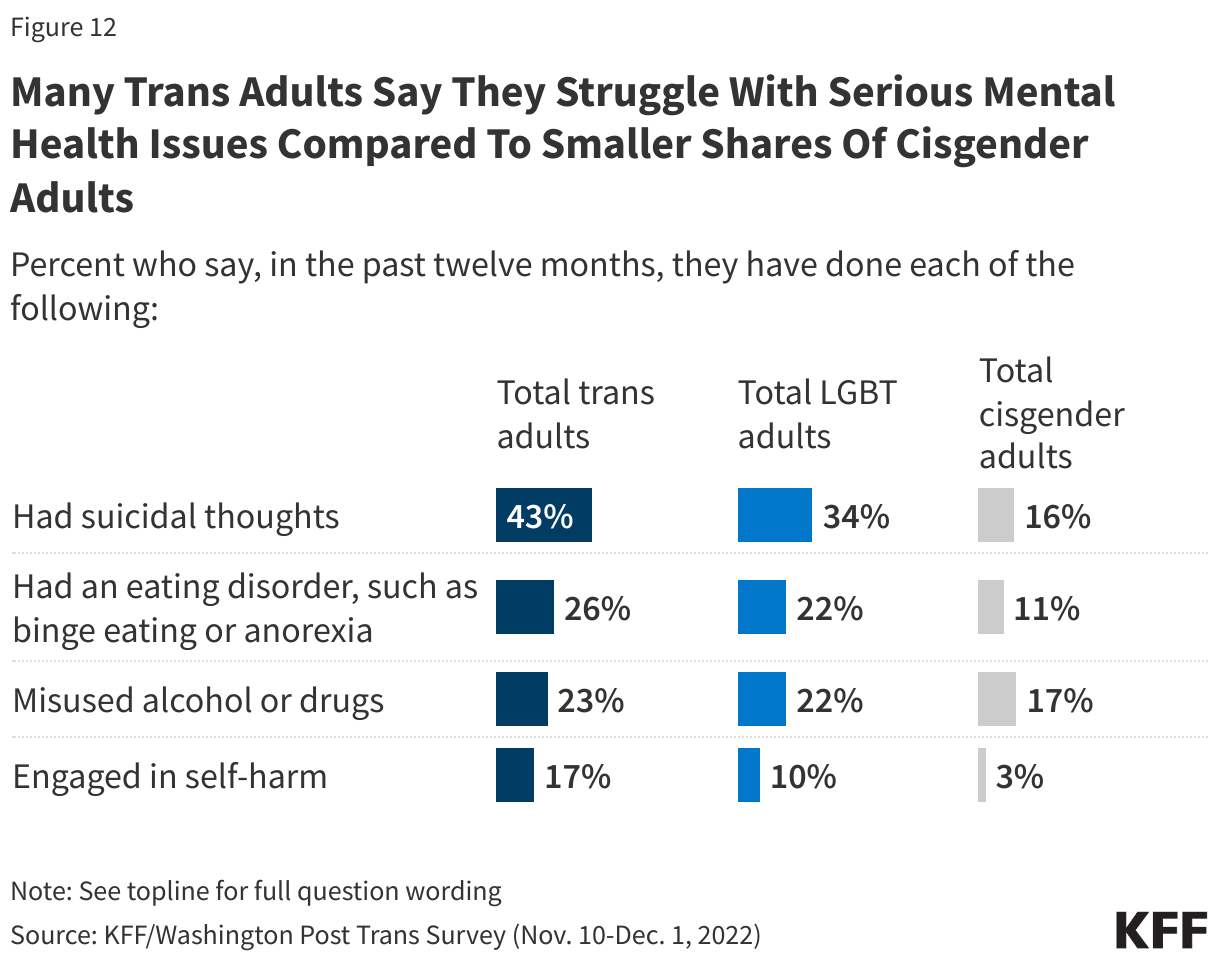
KFF’s polling of trans adults shows that many struggle with serious mental health issues, including 4 in 10 (43%) who say they have had suicidal thoughts in the past year. Trans adults are about six times as likely as cisgender adults to say they have engaged in self-harm in the past year, and more than twice as likely to say they have had an eating disorder in the past year or had suicidal thoughts in the past year. (See Figure 12.)

The figure consists of three groups of stacked bars representing trans adults, LGBT adults, and cisgender adults. It shows the share of each group that has experienced specific mental health challenges including the following in the past 12 months: suicidal thoughts, an eating disorder, misused drugs or alcohol, engaged in self-harm. The chart shows many trans adults struggle with serious mental health issues, at times at higher rates than LGBT people overall, and consistently more commonly than cisgender adults. This includes 43% of trans adults who say they have had suicidal thoughts in the past year compared to 34% of LGBT adults and 16% of cisgender adults and 17% who engaged in self-harm compared to 10% of LGBT adults and 3% of cisgender adults.

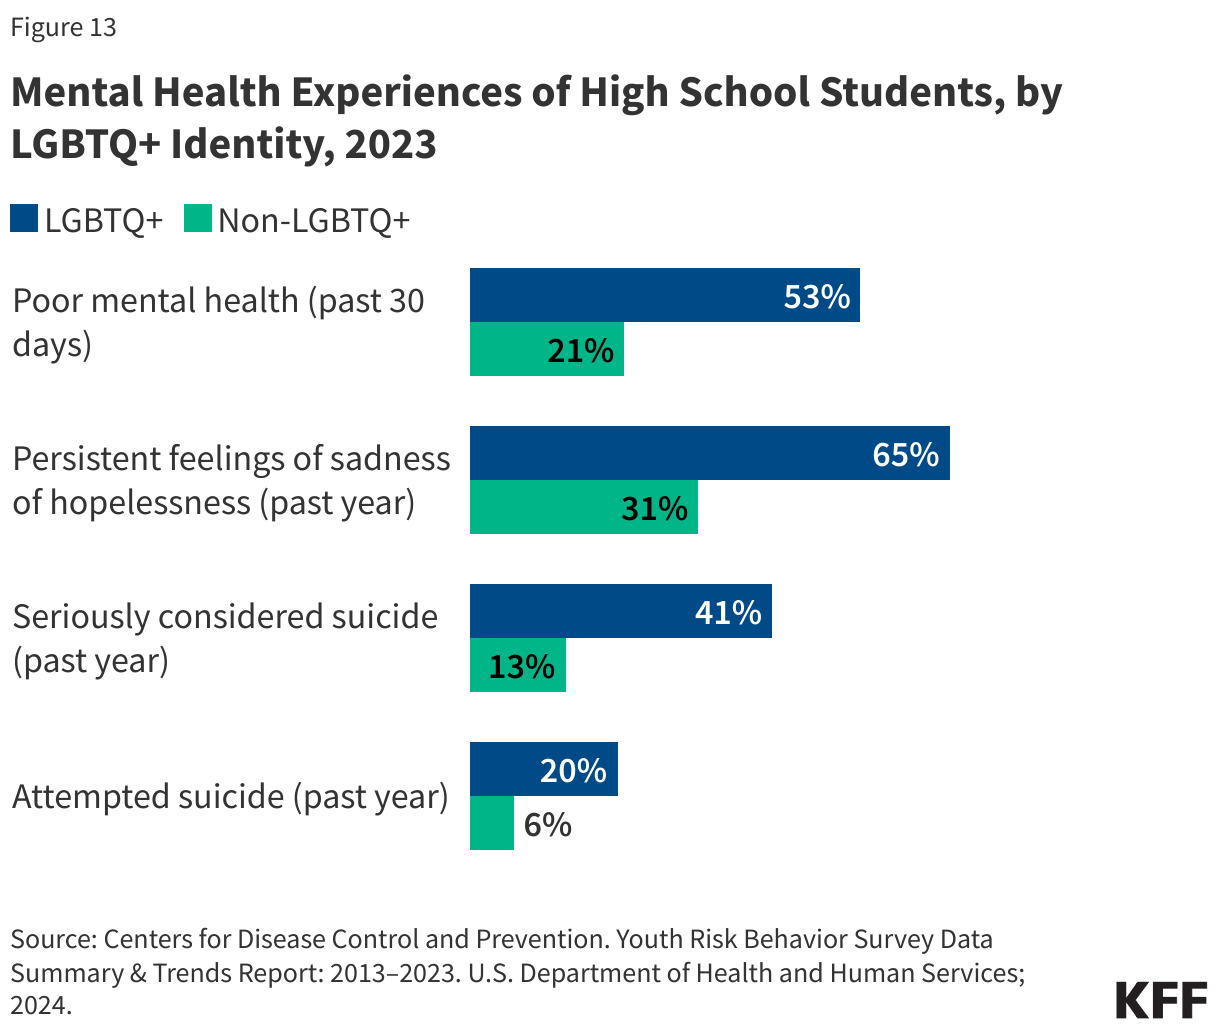
Mental health disparities are especially significant among young LGBTQ+ people. In 2023, more than half (53%) of LGBTQ+ high school students reported poor mental health in the past 30 days compared to 1 in 5 (21%) non-LGBTQ+ students and more than twice as many reported persistent feelings of sadness or hopelessness over the past year (65% among LGBTQ+ students compared to 31% among non-LGBTQ+ students). In addition, 41% of LGBTQ+ high school students reported having seriously considered suicide during the past year, with 20% having attempted suicide, rates that are substantially higher than for non-LGBTQ+ students (13% and 6%, respectively). (See Figure 13.)

A bar chart compares LGBTQ+ and non-LGBTQ+ high school students across several mental health measures. LGBTQ+ students report substantially higher rates of poor mental health in the past 30 days (53% vs. 21%), persistent feelings of sadness or hopelessness during the past year (65% vs. 31%), seriously considering suicide during the past year (41% vs. 13%), and attempting suicide during the past year (20% vs. 6%).

Substance use rates were also higher among LGBTQ+ high school students than their non-LGBTQ+ peers.LGBTQ+ students and students with any same-sex partners were more likely to engage in a range of substance use behaviors than their peers, including use of alcohol, marijuana, any illicit drug, vaping, and prescription opioids.

In addition to higher reported rates of mental health challenges, LGBT people, particularly those in fair or poor mental health and younger adults, report greater challenges accessing mental health care and are more likely to report forgoing needed mental health care than non-LGBT adults. About half (46%) of LGBT adults say there was a time in the past three years when they thought they might need mental health services but didn’t get them, more than twice the share of non-LGBT adults who say so (20%). Reported challenges to care include affordability and accessibility of providers, including finding a provider who can relate to their background and experiences.

Best Practices for Competent Care

Copy link to Best Practices for Competent Care

Access to competent and inclusive health care that meets the needs of LGBTQ+ people can improve engagement with the health system and, ultimately, health outcomes.

The American Medical Association (AMA) provides recommended standards of practice with LGBTQ patients and resources to help make medical practices LGBTQ-friendly, such as including posters, brochures, and other materials that are LGBTQ-inclusive, revising intake materials to be affirming and inclusive, and participating in further provider education.

Similarly, the American Psychiatric Association also provides guidance, including acknowledgment of the role the association played in perpetuating stigma for LGBTQ+ people in the past and guiding practitioners to not make assumptions about sexual orientation or gender identity in gathering medical information, reminding providers that families can be helped to move towards more acceptance of LGBTQ+ children to improve their mental health, and explicitly coming out against ‘conversion or reparative’ therapy. Indeed, the use of “conversion therapy” is condemned among all major health groups, 28 of which signed a 2023 joint statement against its use, stating that such interventions are both ineffective and harmful, and about half of states have enacted a ban on coverage therapy for minors.

Other resources highlight the importance of language use in caring for LGBTQ+ people, including when it comes to how sexual orientation and gender are discussed and described and how patients are addressed with respect to names and pronoun use. Leadership “buy-in” and the role of LGBTQ+ champions are also highlighted, as are the benefits of inclusive policies. Data collection used to improve health outcomes, staff training, and partnering locally with the LGBTQ+ community are also noted as ways to be a more affirming practice.

Providing health care services or competent referrals for health services that are disproportionately needed by the LGBTQ+ community is another way to offer inclusive care. This might include behavioral health services, STI care and screening, or inclusive family planning services. Another such service is gender affirming care (see below).

Gender Affirming Care

Copy link to Gender Affirming Care

Gender affirming care is a model of care which includes a spectrum of “medical, surgical, mental health, and non-medical services for transgender and nonbinary people” aimed at affirming and supporting an individual’s gender identity.Gender affirmation is highly individualized. Not all trans people seek the same types of gender affirming care or services and some people choose not to use medical services as a part of their transition. Gender affirming care is tailored to an individual’s needs across the lifespan.

Virtually all major U.S. medical associations support youth access to gender affirming care, including the American Medical Association, American Academy of Pediatrics, and the American Psychological Association, among others. In particular, these groups point to the evidence demonstrating that medically necessary gender affirming care enhances mental health outcomes for transgender youth, including by reducing suicidal ideation. Professional guidance for gender affirming care, including for young people, is provided by the Endocrine Society and the World Professional Association for Transgender Health, bodies that also support access to this care model.

There is no one way to transition. KFF polling finds commonly utilized gender affirming activities are related to a social transition, such as changing the types of clothes worn (77%), changing hairstyles/grooming habits (76%), or going by different pronouns (72%). Slightly fewer, but still a majority, of trans adults use a different name than the one on their birth certificate (57%). Fewer than half of trans adults report attending counseling or therapy as a part of their gender transition (38%) (which is sometimes a requirement for other gender affirming care), legally changing their name on identifying documents (24%), or using hormone treatments or puberty-blocking hormones (31%) Despite common rhetoric, surgical care is a rare component of gender affirming care, with just 16% of trans adults reporting having received gender-affirming surgery. While the number of young trans people using puberty blockers or hormone therapy has increased modestly in recent years, the overall number of those using these prescriptions remains fairly low and multiple studies have shown gender affirming surgery is extremely rare among minors.

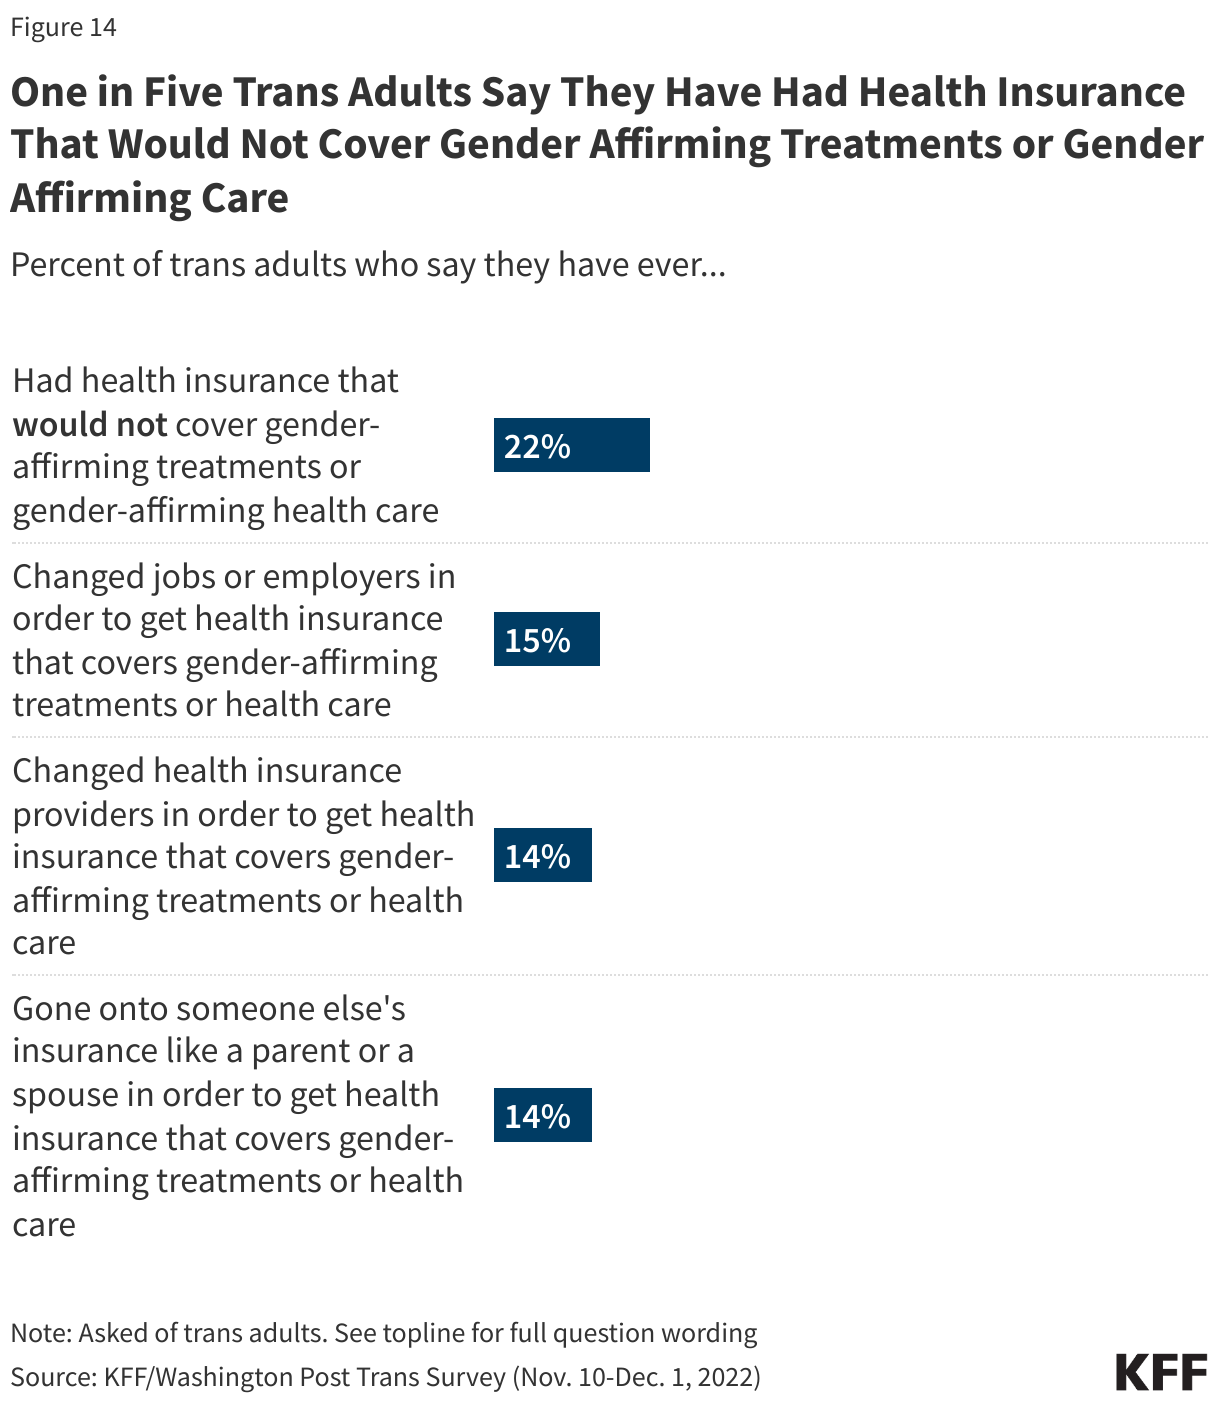
Lack of insurance coverage for gender affirming care is a barrier to receiving these services. KFF’s polling finds, for example, that among trans adults with health insurance, about a quarter (27%) say their insurance covers gender affirming treatment or health care, while 14% say their health insurance does not cover this and 6 in 10 (58%) are unsure. One in 5 trans adults say they have had health insurance that would not cover gender affirming treatments or health care (22%). About 1 in 7 trans adults have changed jobs or health insurance in order to get gender affirming treatments or health care. (See Figure 14.)

This bar chart, titled “One in Five Trans Adults Say They Have Had Health Insurance That Would Not Cover Gender Affirming Treatments or Gender Affirming Care” presents experiences related to insurance coverage for gender-affirming care among trans adults. 22% of trans adults say their insurance would not cover gender-affirming health care, 15% say they have changed jobs or to get insurance covering care, 14% say they changed health insurance providers to get coverage, and 14% say they have gone on someone else’s insurance to get coverage.

Despite the evidence around the role gender affirming care can play in promoting well-being for young people and support from the medical community, some have argued against this care claiming that the services are experimental and lack an evidence base or that young trans people commonly change their minds about their gender identity. The Trump administration, in particular, has moved to limit access to gender affirming care, particularly for youth, through executive orders and other actions (see discussion below). The administration has also promoted misinformation about gender affirming care relating to issues like regret rates, how common surgical care is, and conflating it with female genital mutilation. It has stated that it will seek to prohibit providers receiving federal funding from providing certain gender affirming care services to minors. To date, more than half (27) of US states (as of July 2025) have enacted restrictions on gender affirming care for minors (discussed further below). As a result, young people may be unable to get medically necessary care depending on where they live and the resources their families have. Research has demonstrated that young transgender people’s mental health is negatively impacted when this care is denied, including leading to an increased risk of suicidality. Further, claims around lack of evidence and regret are not borne out by the data and, in fact, the very same services are provided to young people in other medical circumstances without controversy. 

Policy Impact

Copy link to Policy Impact

Policymaking, including in health care, can both facilitate and hinder access to care and coverage, and ultimately, health outcomes, for LGBTQ+ people. Recent examples of how policymaking addresses LGBTQ+ people’s health include:

Supreme Court of the United States (SCOTUS) Decisions: Several recent Supreme Court decisions have impacted the health and well-being of LGBTQ+ people. SCOTUS decisions regarding marriage equality have been particularly far reaching with both the Windsor (2013) and Obergefell (2015) decisions providing same-sex married couples with legal access to spousal health insurance benefits for the first time, among other changes. In Bostock (2019), SCOTUS ruled that in the context of employment, discrimination based on sex encompasses sexual orientation and gender identity—a decision that was subsequently used to support extending sex protections in health care to LGBTQ+ people (see discussion of Section 1557 below). In June 2025, in United States v. Skrmetti, SCOTUS ruled that a Tennessee law banning gender affirming care for minors did not violate the 14th Amendment’s Equal Protection clause, allowing it and other similar laws to remain in place, resulting in a continued patchwork of access. On March 10, 2025, SCOTUS granted certiorari in Chiles v. Salazar and will review a challenge to Colorado's conversion therapy ban for minors, assessing “whether a law that censors certain conversations between counselors and their clients based on the viewpoints expressed regulates conduct or violates the Free Speech Clause.” 

  • Section 1557: One area that has received significant attention over the last decade is Section 1557 of the Affordable Care Act (ACA). Section 1557 prohibits discrimination on the basis of a range of factors, including sex, and applies to health programs and activities receiving federal financial assistance (referred to as covered entities). Specifically, it prevents covered entities from discriminating against certain protected groups in providing health care services, insurance coverage, and program participation. Across different Presidential administrations, lengthy rulemaking and court challenges have affected the application of Section 1557, particularly around whether sexual orientation and gender identity should be encompassed in sex protections. The Obama administration interpreted the statute to include protections on the basis of gender identity and sex-stereotyping, laying out specific protections for trans people, while the Trump administration removed such protections. The Biden administration has since restored and expanded on protections, including by also interpreting sex protections to protect against discrimination on the basis of sexual orientation, following the Bostock decision. As of May 2025, the Trump administration had not yet issued rulemaking on Section 1557, but multiple executive orders suggest that the administration will view sex narrowly, laying the groundwork for removing explicit protections for LGBTQ+ people.
  • Mental Health: Policy can also positively or negatively impact the mental health of the LGBTQ+ community. For example, 988, the federally-mandated suicide and crisis line, supported by the Substance Abuse and Mental Health Services Administration (SAMHSA), historically included specific services to meet the needs of LGBTQ+ young people. While the service represented 10% of all contacts to 988 funded by Congress, the Trump administration ended this service in July 2025. Under the Biden administration, SAMHSA released a “road map” for supporting LGBTQ+ youth, an LGBTQI+ Family Support Grant providing nearly $2 million in funding for programs that address behavioral health for LGBTQ youth, and more than $5 million for “Family Counseling and Support for Lesbian, Gay, Bisexual, Transgender, Queer/Questioning, Intersex+ Youth and their Families,” and also funded the Center of Excellence: LGBTQ+ Behavioral Health Equity aimed at supporting “implementation of change strategies within mental health and substance use disorder treatment systems to address disparities impacting the LGBTQ+ community.” The Biden administration issued a rule to better protect LGBTQ+ youth in foster care. In addition to federal efforts, some states are also electing to highlight and address the behavioral health needs of LGBTQ+ people, sometimes through the use of federal funds. On the other hand, there is evidence that the promulgation of state laws and policies restricting access to LGBTQ+ health and other services negatively affects the mental health of the community. The Trump administration’s approach to LGBTQ people’s health has differed significantly. Following President Trump’s campaign promises, the administration has prioritized actions and policymaking aimed at limiting young people’s access to gender affirming care and, in some cases, denying existence of transgender people and fueling misinformation about transgender and intersex people and trans health care. The administration has reversed Biden-era agendas, roadmaps, and interpretations of civil rights protections regarding LGBTQ people’s well-being. Collectively, these actions can have a negative impact on well-being and access to medically necessary best practice care.
  • Gender affirming care: As noted above, the Trump administration has taken a range of actions and made proposals to limit gender affirming care for minors, differing from the Biden administration which had supported access to this care on principles of equity and well-being. These orders have generally sought to restrict access to services, limit research related to gender diversity, and stated that the federal government will only acknowledge two sexes and will not recognize diverse gender identities, including transgender people. As of July 2025, most of these actions do not formally prohibit entities from providing care, but they have led to a climate of fear and a chilling effect, with many providers walking back gender affirming care services for minors. Actions that led to this include creating an FBI tip line to report clinicians providing surgical care to minors, detailed collection of personal and institutional information offering gender affirming care, issuing subpoenas, and explicitly stating that the administration is seeking to make providing gender affirming care to minors a violation of terms of condition for participation in the Medicare and Medicaid programs, among others. Further actions limiting access are expected, as is litigation challenging these restrictions. The administration also released an evidence review related to information about treatment of gender dysphoria, concluding that the quality of evidence on the effects of intervention is low, and evidence on harms is “sparse.” It also states that there are significant risks and supports the use of psychotherapeutic approaches, including an approach termed “exploratory therapy”, which can include conversion therapy, departing from most U.S. medical associations. While the report has been used to promote restrictions, it has also faced criticism including for its approach to the review and promotion of misinformation, among other factors. Impacting both adults and minors, the administration also adopted a policy that would not require broad financial protections in the individual market and small group health insurance marketplaces from applying to gender affirming care.
  • Data collection: (See also callout box on data collection.)Better understanding who the LGBTQ+ community is and what challenges they face allows policymakers, providers, and other individuals and groups to meet their needs better and provide care and coverage that is culturally competent. Addressing care needs may happen in the provider’s office, at the health system level, or in the policy arena. Research on LGBTQ+ people and health has generally increased over time though that trend is currently reversing at the federal level. Both the Obama and Biden administrations implemented a range of efforts to improve collection and reporting of data on LGBTQ+ people. For example, in 2016, the NIH designated sexual and gender minorities (SGMs) as a health disparity population for research purposes. In doing so, NIH recognized the health disparities faced by this population and that “the extent and causes of health disparities are not fully understood, and research on how to close these gaps is lacking.” Many federal surveys also began to ask sexual orientation and gender identity (SOGI) questions, including the Behavioral Risk Factor Surveillance System Survey, the National Survey on Drug Use, the National Health Interview Survey, and the Youth Risk Behavior Survey, though data collection was not routine and it was sometimes an optional variable for states or a restricted variable for researchers. The Biden administration also issued an executive order calling for agencies to enhance routine collection of SOGI data to improve outcomes and address disparities, and an implementing roadmap in a Federal Evidence Agenda. However, SOGI data collection has become politicized. The first Trump administration sought to roll back some of the activities of the Obama administration, and these efforts have intensified in President Trump’s second term. On his first day in office President Trump rescinded the Biden-era executive order on data collection and issued executive orders taking a narrow view of sex and removing recognition of gender identity and limiting diversity, equity, inclusion, and accessibility (DEIA) activities in government programs, which led to limiting data collection efforts. A range of datasets, questionnaires, codebooks, reports, and other documents were removed from federal websites in the early days of the administration (some of which have been reposted due to a court order)and SOGI data collection in major surveys, including the Census, have been discontinued to comply with executive orders. Beyond survey data, data collection is also limited by efforts to rescind LGBTQ related research funding. Data collection efforts are also variable at state and health system levels and, if not reliant on federal funding, may be able to continue.
  • State and Local Policymaking: While federal policymaking plays an important role in individuals’ lives, so too does state and local policymaking, perhaps, especially so in health care. Over the past few years, there has been a rash of policymaking addressing LGBTQ+ people’s health. Policies have both aimed to expand protections and well-being for LGBTQ+ people and sought to restrict access to care or loosen antidiscrimination standards. For example, as of July 2025, over half of states have enacted policies aimed at limiting or prohibiting youth access to gender affirming care and most of this policymaking took place within an 18-month period . Other states have enacted “refuge laws” (also known as “shield laws”) that generally aim to protect individuals, families, and providers living in states where these bans have been enacted. State policymaking has also focused on LGBTQ+ people and access to services through private and public insurance coverage. For example, while some states expressly prohibit insurers from discriminating against people based on sexual orientation and gender identity, others are silent on the issue. Similarly, some state Medicaid programs explicitly cover gender affirming care, others have exclusions, and some have no clear policy; even those that do cover this care may not cover all the services an individual needs. About half of states have enacted laws banning conversion therapy for minors, but the Supreme Court is set to hear a challenge to Colorado’s ban in the fall of 2025. Finally, some LGBTQ+ related policy is not overtly health-related but has the potential to impact well-being. For example, preventing schools from adopting LGBTQ+ anti-bullying policies or enacting laws that require school staff to out transgender youth to their families stand to negatively impact health outcomes.

Future Outlook

Copy link to Future Outlook

Despite the increase in the share of people identifying as LGBTQ+ and in public support for LGBTQ+ relationships and protections against discrimination, LGBTQ+ people continue to face health disparities and worse health outcomes in several areas. In many cases, these are directly related to ongoing experiences of stigma, discrimination, and violence. Policy efforts to address health disparities among LGBTQ+ people, including those tied to experiences of stigma and discrimination, had increased over time but under the second Trump administration are reversing, with numerous executive branch actions designed to limit access to care and remove protections for LGBTQ+ people.  More generally, there has been growing partisanship in some areas of LGBTQ+ rights and access, particularly for LGBTQ+ youth, and a rise in the number of policies and laws that restrict access to recommended care. Monitoring these policies, the shifting legal landscape, and better understanding the actual experiences of LGBTQ+ people will help inform efforts to address and mitigate health disparities for this population moving forward.

Resources

Copy link to Resources

Citation

Copy link to Citation

Dawson, L., Kates, J., Montero, A., and Kirzinger, A., LGBTQ+ Health Policy. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-lgbtq-health-policy/ (date accessed).

Congress and the Executive Branch and Health Policy

KFF Author:

Table of Contents

Introduction

Copy link to Introduction

The federal government is not the only place health policy is made in the U.S., but it is by far the most influential. Of the $4.9 trillion the U.S. spent on health in 2023, the federal government was responsible for roughly a third of all health services. The payment and coverage policies set for the Medicare program, in particular, often serve as a model for the private sector. Many health programs at the state and local levels are also impacted by federal health policy, either through direct spending or rules and requirements. Federal health policy is primarily guided by Congress, but carried out by the executive branch, predominantly by the Department of Health and Human Services. 

The Federal Role in Health Policy 

Copy link to The Federal Role in Health Policy 

No one is “in charge” of the fragmented U.S. health system, but the federal government probably has the most influence, a role that has grown over the last 75 years. Today the federal government pays for care, provides it, regulates it, and sponsors biomedical research and medical training.  

The federal government pays for health coverage for well over 100 million Americans through Medicare, Medicaid, the Children’s Health Insurance Program (CHIP), the Veterans’ Health Administration, the Indian Health Service, and the Affordable Care Act (ACA).  It also pays to help provide insurance coverage for tens of millions who are active-duty and retired military and for civilian federal workers.

Federal taxpayers also underwrite billions of dollars in health research, mainly through the National Institutes of Health (NIH) and the Agency for Healthcare Research and Quality (AHRQ).

Federal public health policy is spearheaded by the Centers for Disease Control and Prevention. Its portfolio includes tracking not just infectious disease outbreaks in the U.S. and worldwide, but also conducting and sponsoring public health research and tracking national health statistics. 

The Health Resources and Services Administration (HRSA) funds critical health programs for underserved Americans (including Community Health Centers) and runs workforce education programs to bring more health services to places without enough health care providers. 

Meanwhile, in addition to overseeing the nation’s largest health programs, the Centers for Medicare and Medicaid Services (CMS) also operates the federal insurance Marketplaces created by the ACA and enforces rules made by the law for private insurance policies. 

While the federal government exercises significant authority over medical care and its practice and distribution, state and local governments still have key roles to play.  

States oversee the licensing of health care professionals, distribution of health care resources, and regulation of health insurance plans that are not underwritten by employers themselves. State and local governments share responsibility for most public health activities and often operate safety-net facilities in areas with shortages of medical resources. 

The Three Branches of Government and How They Impact Health Policy 

Copy link to The Three Branches of Government and How They Impact Health Policy 

All three branches of the federal government – Congress, the executive branch, and the judiciary – play important roles in health policy. 

Congress makes laws that create new programs or modify existing ones. It also conducts “oversight” of how the executive branch implements the laws Congress has passed. Congress also sets the budget for “discretionary” and “mandatory” health programs (see below) and provides those dollar amounts. 

The executive branch carries out the laws made by Congress and operates the federal health programs, often filling in details Congress has left out through rules and regulations. Federal workers in the health arena may provide direct patient care, regulate how others provide care, set payment rates and policies, conduct medical or health systems research, regulate products sold by the private sector, and manage the billions of dollars the federal government spends on the health-industrial complex.  

Historically, the judiciary has had the smallest role in health policy, but has played a pivotal role in recent cases. It passes judgment on how or whether certain laws or policies can be carried out and settles disputes between the federal government, individuals, states, and private companies over how health care is regulated and delivered.  Recent significant decisions from the Supreme Court have affected the legality and availability of abortion and other reproductive health services and the constitutionality of major portions of the ACA.

The Executive Branch – The White House

Although most of the executive branch’s health policies are implemented by the Department of Health and Human Services (and to a smaller extent, the Departments of Labor and Justice), over the past several decades the White House itself has taken on a more prominent role in policy formation. The White House Office of Management and Budget not only coordinates the annual funding requests for the entire executive branch, but it also reviews and approves proposed regulations, Congressional testimony, and policy recommendations from the various departments. The White House also has its own policy support agencies – including the National Security Council, the National Economic Council, the Domestic Policy Council, and the Council of Economic Advisors – that augment what the President receives from other portions of the executive branch.

How the Department of Health and Human Services is Structured

Copy link to How the Department of Health and Human Services is Structured

Most federal health policy is made through the Department of Health and Human Services. Exceptions include the Veterans Health Administration, run by the Department of Veterans Affairs; TRICARE, the health insurance program for active-duty military members and dependents, run by the Defense Department; and the Federal Employees Health Benefits Program (FEHB), which provides health insurance for civilian federal workers and families and is run by the independent agency the Office of Personnel Management.  

The health-related agencies within HHS are roughly divided into the resource delivery, research, regulatory, and training agencies that comprise the U.S. Public Health Service and the health insurance programs run by the Centers for Medicare and Medicaid Services (CMS). 

Ten of the 13 operating divisions of HHS are part of the U.S. Public Health Service, which also plays a role in U.S. global health programs. They are: 

  • The Administration for Strategic Preparedness and Response (ASPR) 
  • The Advanced Research Projects Agency for Health (ARPA-H)
    • The Agency for Healthcare Research and Quality (AHRQ) 
    • The Agency for Toxic Substances and Disease Registry (ATSDR) 
    • The Centers for Disease Control and Prevention (CDC) 
    • The Food and Drug Administration (FDA) 
    • The Health Resources and Services Administration (HRSA) 
    • The Indian Health Service (IHS) 
    • The National Institutes of Health (NIH) 
    • The Substance Abuse and Mental Health Services Administration (SAMHSA) 

The Centers for Medicare and Medicaid Services (CMS) is by far the largest operating division of HHS. It oversees not just the Medicare and Medicaid programs, but also the federal Children’s Health Insurance Program (CHIP) and the health insurance portions of the Affordable Care Act. Together, the programs under the auspices of CMS account for nearly a quarter of all federal spending in fiscal 2023, cost an estimated $1.5 trillion in fiscal 2023, and served more than 170 million Americans – more than half the population.

The current Trump administration has proposed a major restructuring of the health agencies under HHS, including creation of a new “Administration for a Healthy America.” As of September 2025, that restructuring has been blocked by court action.  However, a data analysis conducted by the news organization ProPublica found that as of August 2025, more than 20,500 workers – about 18 percent of the department’s workforce – had been laid off or left their jobs.

Who Makes Health Policy in Congress?

Copy link to Who Makes Health Policy in Congress?

How Congress oversees the federal health care-industrial complex is almost as byzantine as the U.S. health system itself. Jurisdiction and responsibility for various health agencies and policies is divided among more than two dozen committees in the House and Senate (Tables 1 and 2). 

In each chamber, however, three major committees deal with most health issues.  

In the House, the Ways and Means Committee, which sets tax policy, oversees Part A of Medicare (because it is funded by the Social Security payroll tax) and shares jurisdiction over other parts of the Medicare program with the Energy and Commerce Committee. Ways and Means also oversees tax subsidies and credits for the Affordable Care Act and tax policy for most employer-provided insurance.  

The Energy and Commerce Committee has sole jurisdiction over the Medicaid program in the House and shares jurisdiction over Medicare Parts B, C, and D with Ways and Means. Energy and Commerce also oversees the U.S. Public Health Service, whose agencies include the Food and Drug Administration, the National Institutes of Health, and the Centers for Disease Control and Prevention.  

While Ways and Means and Energy and Commerce are in charge of the policymaking for most of the federal government’s health programs, the actual amounts allocated for many of those programs are determined by the House Appropriations Committee through the annual Labor-Health and Human Services-Education and Related Agencies spending bill.  

In the Senate, responsibility for health programs is divided somewhat differently. The Senate Finance Committee, which, like House Ways and Means, is in charge of tax policy, oversees all of Medicare and Medicaid and most of the ACA.  

The Senate counterpart to the House Energy and Commerce Committee is the Senate Health, Education, Labor and Pensions Committee, which has jurisdiction over the Public Health Service (but not Medicare or Medicaid).  

The Senate Appropriations Committee, like the one in the House, sets actual spending for discretionary programs as part of its annual Labor-HHS-Education spending bill. 

Senate Committees with Health Jurisdiction
House Committees with Health Jurisdiction

The Federal Budget Process

Copy link to The Federal Budget Process

Under Article 1 of the U.S. Constitution, Congress is granted the exclusive power to “lay and collect Taxes, Duties, Imposts and Excises, and to pay the Debts and provide for the common Defence and General Welfare of the United States.”  

In 1974, lawmakers passed the Congressional Budget and Impoundment Control Act in an effort to standardize the annual process for deciding tax and spending policy for each federal fiscal year and to prevent the executive branch from making spending policy reserved to Congress. Among other things, it created the House and Senate Budget Committees and set timetables for each step of the budget process.  

Perhaps most significantly, the 1974 Budget Act also created the Congressional Budget Office (CBO). This non-partisan agency has come to play a pivotal role in not just the budget process, but in the lawmaking process in general. The CBO issues economic forecasts, policy options, and other analytical reports, but it most significantly produces estimates of how much individual legislation would cost or save the federal government. Those estimates can and do often determine if legislation passes or fails.

The annual budget process is supposed to begin the first Monday in February, when the President is to present his proposed budget for the fiscal year that begins the following Oct. 1. This is one of the few deadlines in the Budget Act that is usually met. 

After that, the action moves to Congress. The House and Senate Budget Committees each write their own “Budget Resolution,” a spending blueprint for the year that includes annual totals for mandatory and discretionary spending. Because mandatory spending (roughly two-thirds of the budget) is automatic unless changed by Congress, the budget resolution may also include “reconciliation instructions” to the committees that oversee those programs (also known as “authorizing” committees) to make changes to bring the cost of the mandatory programs in line with the terms of the budget resolution. The discretionary total will eventually be divided by the House and Senate Appropriations Committees between the 12 subcommittees, each responsible for a single annual spending (appropriations) bill. Most of those bills cover multiple agencies – the appropriations bill for the Department of Health and Human Services, for example, also includes funding for the Departments of Labor and Education.  

After the budget resolution is approved by each chamber’s Budget Committee, it goes to the House and Senate floor, respectively, for debate. Assuming the resolutions are approved, a “conference committee” comprised of members from each chamber is tasked with working out the differences between the respective versions. A final compromise budget resolution is supposed to be approved by both chambers by April 15 of each year. (This rarely happens.) Because the final product is a resolution rather than a bill, the budget does not go to the President to sign or veto.  

The annual appropriations process kicks off May 15, when the House may start considering the 12 annual spending bills for the fiscal year that begins Oct. 1. By tradition, spending bills originate in the House, although sometimes, if the House is delayed in acting, the Senate will take up its own version of an appropriation first. The House is supposed to complete action on all 12 spending bills by June 30, in order to provide enough time to let the Senate act, and for a conference committee to negotiate a final version that each chamber can approve by October 1. 

That October 1 deadline is the only one with consequences if it is not met. Unless an appropriations bill for each federal agency is passed by Congress and signed by the President by the start of the fiscal year, that agency must shut down all “non-essential” activities funded by discretionary spending until funding is approved. Because Congress rarely passes all 12 of the appropriations bills by the start of the fiscal year (the last time was in 1996, for fiscal year 1997), it can buy extra time by passing a “continuing resolution” (CR) that keeps money flowing, usually at the previous fiscal year’s level. CRs can last as little as a day and as much as the full fiscal year and may cover all of the federal government (if none of the regular appropriations are done) or just the departments for the unfinished bills. Congress may, and frequently does, pass multiple CRs while it works to complete the appropriations process. 

While each appropriations bill is supposed to be considered individually, to save time (and sometimes to win needed votes), a few, several, or all the bills may be packaged into a single “omnibus” measure. Bills that package only a handful of appropriations bills are cheekily known as “minibuses.”  

Meanwhile, if the budget resolution includes reconciliation instructions, that process proceeds on a separate track. The committees in charge of the programs requiring alterations each vote on and report their proposals to the respective budget committees, which assemble all of the changes into a single bill. At this point, the budget committees’ role is purely ministerial; it may not change any of the provisions approved by the authorizing committees.  

Reconciliation legislation is frequently the vehicle for significant health policy changes, partly because Medicare and Medicaid are mandatory programs. Reconciliation bills are subject to special rules, notably on the Senate floor, which include debate time limitations (no filibusters) and restrictions on amendments. Reconciliation bills also may not contain provisions that do not pertain directly to taxing or spending. 

Unlike the appropriations bills, nothing happens if Congress does not meet the Budget Act’s deadline to finish the reconciliation process, June 15. In fact, in more than a few cases, Congress has not completed work on reconciliation bills until the calendar year AFTER they were begun.   

A (Very Brief) Explanation of the Regulatory Process

Copy link to A (Very Brief) Explanation of the Regulatory Process

Congress writes the nation’s laws, but it cannot account for every detail in legislation. So, it often leaves key decisions about how to interpret and enforce those laws to the various executive departments. Those departments write (and often rewrite) rules and regulations according to a very stringent process laid out by the 1946 Administrative Procedure Act (APA). The APA is intended to keep the executive branch’s decision-making transparent and to allow public input into how laws are interpreted and enforced.

Most federal regulations use the APA’s “informal rulemaking” process, also known as “notice and comment rulemaking,” which consists of four main parts: 

  • Publication of a “Notice of Proposed Rulemaking (NPRM)” in the Federal Register, a daily publication of executive branch activities. 
  • Solicitation to the public to submit written comments for a specific period of time (usually from 30 to 90 days). 
  • Agency consideration of public reaction to the proposed rule; and, finally 
  • Publication of a final rule, with an explanation including how the agency took the public comments into account and what changes, if any, were made from the proposed rule. Final rules also include an effective date, which can be no less than 30 days but may be more than a year in the future. 

In situations where time is of the essence, federal agencies may truncate that process by issuing “interim final rules,” which can take effect even before the public is given a chance to comment. Such rules may or may not be revised later.  

Not all federal interpretation of laws uses the APA’s specified regulatory process. Federal officials also distribute guidance, agency opinions, or “statements of policy.” 

Future Outlook

Copy link to Future Outlook

Given how fragmented health policy is in both Congress and the executive branch, it should not be a surprise that major changes are difficult and rare.  

Add to that an electorate divided over whether the federal government should be more involved or less involved in the health sector, and huge lobbying clout from various interest groups whose members make a lot of money from the current operation of the system, and you have a prescription for inertia. 

Sometimes change does happen suddenly, however. In 2025, Republicans in control of the House, Senate, and White House narrowly passed a budget reconciliation bill that is projected to make deep cuts to the Medicaid program as well as add new barriers for people to maintain or enroll in health insurance under the ACA.

Another potential wildcard—in June of 2024, the Supreme Court overturned a 40-year-old precedent, known as “Chevron deference,” that gave the benefit of the doubt in interpreting ambiguous laws passed by Congress to federal agencies rather than judges. Overturning Chevron will likely make it easier for outsiders to challenge federal agency actions, but it will be some time before the full ramifications become clear.   

Another problem is that when a new health policy can dodge the minefield of obstacles to become law, it almost by definition represents a compromise that may help it win enough votes for passage, but is more likely to complicate an already byzantine system further. 

Unless the health system completely breaks down, it seems unlikely that federal policymakers will be able to move the needle very far in either a conservative or a liberal direction, although the second Trump administration is attempting to circumvent Congress entirely to remake federal health agencies and how they work. Whether that will withstand review by the courts remains to be seen.

Resources

Copy link to Resources

Citation

Copy link to Citation

Rovner, J., Congress, the Executive Branch, and Health Policy. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-congress-and-the-executive-branch-and-health-policy/ (date accessed).

The Politics of Health Care and Elections

Table of Contents

Introduction

Copy link to Introduction

Health policy and politics are inextricably linked. Policy is about what the government can do to shift the financing, delivery, and quality of health care, so who controls the government has the power to shape those policies.

Elections, therefore, always have consequences for the direction of health policy – who is the president and in control of the executive branch, which party has the majority in the House and the Senate with the ability to steer legislation, and who has control in state houses. When political power in Washington is divided, legislating on health care often comes to a standstill, though the president still has significant discretion over health policy through administrative actions. And, stalemates at the federal level often spur greater action by states.

Health care issues often, but not always, play a dominant role in political campaigns. Health care is a personal issue, so it often resonates with voters. The affordability of health care, in particular, is typically a top concern for voters, along with other pocketbook issues, and, at over 17% of the economy, health care has many industry stakeholders who seek influence through lobbying and campaign contributions. At the same time, individual policy issues are rarely decisive in elections.

Health Reform in Elections

Copy link to Health Reform in Elections

Health “reform” – a somewhat squishy term generally understood to mean proposals that significantly transform the financing, coverage, and delivery of health care – has a long history of playing a major role in elections.

Harry Truman campaigned on universal health insurance in 1948, but his plan went nowhere in the face of opposition from the American Medical Association and other groups. While falling short of universal coverage, the creation of Medicare and Medicaid in 1965 under Lyndon Johnson dramatically reduced the number of uninsured people. President Johnson signed the Medicare and Medicaid legislation at the Truman Library in Missouri, with Truman himself looking on.

Later, Bill Clinton campaigned on health reform in 1992, and proposed the sweeping Health Security Act in the first year of his presidency. That plan went down to defeat in Congress amidst opposition from nearly all segments of the health care industry, and the controversy over it has been cited by many as a factor in Democrats losing control of both the House and the Senate in the 1994 midterm elections.

For many years after the defeat of the Clinton health plan, Democrats were hesitant to push major health reforms. Then, in the 2008 campaign, Barack Obama campaigned once again on health reform, and proposed a plan that eventually became the Affordable Care Act (ACA). The ACA ultimately passed Congress in 2010 with only Democratic votes, after many twists and turns in the legislative process. The major provisions of the ACA were not slated to take effect until 2014, and opposition quickly galvanized against the requirement to have insurance or pay a tax penalty (the “individual mandate”) and in response to criticism that the legislation contained so-called “death panels” (which it did not). Republicans took control of the House and gained a substantial number of seats in the Senate during the 2010 midterm elections, fueled partly by opposition to the ACA.

The Affordable Care Act (Obamacare)

Copy link to The Affordable Care Act (Obamacare)

The ACA took full effect in 2014, with millions gaining coverage, but more people viewed the law unfavorably than favorably, and repeal became a Republican rallying cry in the 2016 campaign. After the election of Donald Trump, a high-profile effort to repeal the law was ultimately defeated following a public backlash. The ACA repeal debate was a good example of the trade-offs inherent in all health policies. Republicans sought to reduce federal spending and regulation, but the result would have been fewer people covered and weakened protections for people with pre-existing conditions. KFF polling showed that the ACA repeal effort led to increased public support for the law, which persists today.

KFF Health Tracking Poll: The Public's Views on the ACA

While President Trump failed in his first term to repeal the ACA, his administration repealed the individual mandate penalty, reduced federal funding for consumer assistance (navigators) by 84% and outreach by 90%, and expanded short-term insurance plans that can exclude coverage of preexisting conditions.

In a strange policy twist, the Trump administration ended payments to ACA insurers to compensate them for a requirement to provide reduced cost sharing for low-income patients. But, insurers responded by increasing premiums, which in turn increased federal premium subsidies and federal spending, likely strengthening the ACA.

Between President Trump’s presidential terms, the Biden administration restored outreach funding and signed legislation increasing the premium tax credits that help ACA Marketplace enrollees pay their premiums, leading to record enrollment and historically low uninsured rates.

The increased premium tax credits are set to expire at the end of 2025 unless Congress and President Trump take action. If these tax credits do expire, people purchasing subsidized coverage will face significant increases in their monthly premium payments and some may become priced out of the market.

President Trump’s second term has already brought federal policy changes that will significantly alter ACA Marketplace operations, consumer protections, and premium tax credit eligibility. Key changes in the 2025 budget reconciliation law, such as ending auto-renewals, removing repayment limits for tax credits when income rises, and tightening eligibility verification, are projected by the Congressional Budget Office (CBO) to result in 2 million people becoming uninsured.

Medicaid

Copy link to Medicaid

Since its establishment in 1965, Medicaid has evolved as states took up the optional joint federal-state program to the point that in the 1980s all 50 states were participating. Due to the nature of its federal and state management, there has been a give-and-take over the flexibility of and spending for the program, but it has generally expanded in its coverage of key population groups.

With the passage of the ACA, Medicaid experienced its largest federal policy coverage expansion with the addition of what was ultimately a state option to cover adults with incomes up to 138% of the federal poverty level in exchange for enhanced federal funding for the coverage. Much like the take-up of the original Medicaid program, states have gradually adopted the expansion so that only 10 states, mainly concentrated in the South, remain holdouts. However, recent federal actions may alter the expansion landscape.

Until 2025, the most serious attempt by federal policymakers to make cuts to the Medicaid program was during the 2017 failed attempt to repeal the ACA. Medicaid changes in the legislation included a rollback of enhanced federal matching funds for the Medicaid expansion and a per-enrollee cap of federal funds for most Medicaid enrollees. The 2025 budget reconciliation law includes the largest enacted cuts in Medicaid’s history, instituting Medicaid work requirements, tightening eligibility checks and reducing or capping types of provider funding. The CBO estimates that 7.5 million people will become uninsured due to the Medicaid provisions of the law. However, several of the Medicaid provisions will not be implemented until after the 2026 midterm elections.

Affordability of Health Care

Copy link to Affordability of Health Care

One persistent feature of health care as an election issue is that it is fundamentally an economic issue for the country and for individuals. If you are uninsured, you not only experience access issues, but also the high cost of health care treatment. If you have health insurance, you worry about annual premium changes, deductibles, and cost-sharing related to health care services and prescription drugs whose prices continue to rise.

President Trump has often spotlighted the high price of prescription drugs, criticizing both the pharmaceutical industry and pharmacy benefit managers. Although he kept the issue of drug prices on the political agenda as president, in the end, his first administration accomplished little to restrain them. 

President Biden signed the Inflation Reduction Act, which requires the federal government to negotiate the prices of certain drugs in Medicare, which was previously banned. How aggressively the prescription drug negotiation program proceeds during the second Trump administration is an open question. While President Trump has issued an executive order calling for a “most favored nation” policy for drug pricing, with prices in the U.S. matching the currently lower prices in other countries, it remains unclear how drug companies will respond to the call and whether there will be any enforcement mechanism.

Health Care Infrastructure of the Federal Government

Copy link to Health Care Infrastructure of the Federal Government

A feature of the second Trump administration has been the push to remake the executive branch of the federal government to reflect his priorities at a scale that hasn’t occurred in the recent past. Secretary of Health and Human Services (HHS), Robert F. Kennedy, Jr., announced a plan to restructure the department in March 2025 that would reduce the workforce substantially, create the new agency Administration for a Healthy America, reorganize and consolidate divisions and relocate offices.

HHS Secretary Kennedy is also leading the Make America Healthy Again (MAHA) Commission and making substantial changes to the vaccine approval process by remaking the roster for the Centers for Disease Control and Prevention’s Advisory Committee on Immunization Practices and having CDC change recommendations for who should receive the COVID-19 vaccine.

These changes to the federal health care infrastructure could impact the accessibility of vaccines and other preventive services, as well as undermine the confidence the public has in the government, particularly its scientific agencies.

Future Outlook

Copy link to Future Outlook

Ultimately, irrespective of the issues that get debated during the campaign, the outcome of federal elections – who controls the White House and Congress – has significant implications for the future direction of health care.

However, even with changes in party control of the federal government, generally incremental movement to the left or the right is the norm. Sweeping changes in health policy, such as the creation of Medicare and Medicaid or passage of the ACA, are rare in the U.S. political system and are usually preceded by one-party control of Congress and the presidency. More fundamental changes in health care financing and coverage, such as Medicare for All, face long odds. This is the case even though most of the public favors Medicare for All, though attitudes shift significantly after hearing messages about its potential impacts.

It has historically been politically difficult to take benefits away from people once they have them. That, and the fact that seniors are a strong voting bloc, has been why Social Security and Medicare have been considered political “third rails.” While Medicare and Social Security were largely untouched in the Republican tax and spending law passed in 2025, the law made substantial cuts to the ACA and Medicaid, and millions more people are projected to become uninsured in what will be the biggest rollback in federal support for health coverage ever. Looking toward the 2026 midterm election and beyond, changes to both the ACA and Medicaid, as well as fundamental changes to the health care infrastructure and public health policies of the federal government, may emerge as major campaign issues.

Resources

Copy link to Resources

Citation

Copy link to Citation

Levitt, L. & Singh, R., The Politics of Health Care and the 2024 Election. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/elections/health-policy-101-the-politics-of-health-care-and-elections/ (date accessed).

The Affordable Care Act 101

Table of Contents

What Is the Affordable Care Act?

Copy link to What Is the Affordable Care Act?

On March 23, 2010, President Obama signed the Affordable Care Act (ACA) into law, marking a significant overhaul of the U.S. health care system. Prior to the ACA, high rates of uninsurance were prevalent due to unaffordability and exclusions based on preexisting conditions. Additionally, some insured people faced extremely high out-of-pocket (OOP) costs and coverage limits. The ACA aimed to address these issues, though it did not eliminate all of them.

The ACA affects virtually all aspects of the health system, including insurers, providers, state governments, employers, taxpayers, and consumers. The law built on the existing health insurance system, making changes to Medicare, Medicaid, and employer-sponsored coverage. A fundamental change was the introduction of regulated health insurance exchange markets, or Marketplaces, which offer financial assistance for ACA-compliant coverage to those without traditional insurance sources. This chapter has a special focus on these Marketplaces that are integral to the ACA’s framework.

What Did the ACA Change About Health Coverage in the U.S.?

Copy link to What Did the ACA Change About Health Coverage in the U.S.?

A key goal of the ACA was to expand health insurance coverage. It did so by expanding Medicaid to people with incomes up to 138% of the federal poverty level (the poverty level in the continental U.S. is $15,650 for a single individual in 2025); creating new health insurance exchange markets through which individuals can purchase coverage and receive financial help to afford premiums and cost sharing, in addition to separate exchange markets through which small businesses can purchase coverage; and requiring employers that do not offer affordable coverage to pay penalties, with exceptions for small employers. In the years leading up to the passage of the ACA, about 14-16% of people in the United States were uninsured (across all ages). By 2023, the uninsured rate had fallen to a record low of 7.7%. Most of the gains in insurance coverage have come from the ACA’s expansion of Medicaid, followed by the creation of the exchange markets.

For people with private health insurance, the ACA also includes several consumer protections and market rules (discussed in more detail in the chapter on regulation of private insurance). For example, the ACA prohibits health plans from denying people coverage, charging them higher premiums, as well as rescinding or imposing exclusions to coverage due to preexisting health conditions. The ACA also prohibits annual and lifetime limits on the dollar amount of coverage and restricts the amount of out-of-pocket costs individuals and families may incur each year for in-network care. Additionally, the law requires most health plans to cover preventive health services with no out-of-pocket costs. Health insurers must also issue rebates to enrollees and businesses each year if they fail to meet Medical Loss Ratio standards. Moreover, people with private coverage can keep their young adult children on their health plan up to age 26.

The ACA imposes additional new regulations on private health plans sold to individuals and small businesses. These rules significantly limit the ways in which health plans can charge higher premiums. ACA-compliant health plans sold on the individual and small group markets can only vary premiums based on location, family size, tobacco use, and age (with older adults being charged no more than three times younger adults). This means that people with preexisting conditions cannot be charged higher premiums, nor can insurers charge higher rates based on gender or other factors. The ACA requires individual and small group insurers planning to increase premiums significantly to justify those rate increases publicly and also included grants for states to improve their rate review programs. The ACA also created risk programs in the individual and small group markets to mitigate adverse selection and to reduce health insurers’ incentives to avoid attracting sicker enrollees.

Federal Law Market Rules for Private Health Insurance Sold to Individuals And Groups (Table)

While Medicaid expansion is one of the most impactful provisions of the ACA, the law changed Medicaid in other ways too. For example, people gaining coverage through the Medicaid expansion are guaranteed a benchmark benefit package that covers essential health benefits. Furthermore, the ACA required state Medicaid programs to cover preventive services without cost sharing. The law also increased Medicaid payments to primary care providers, provided new options for states to cover in-home and community-based care, increased Medicaid drug rebates, and extended those rebates to Medicaid managed care plans.

The ACA also made a number of changes to Medicare. Notably, the ACA phased out the Medicare Part D prescription drug benefit coverage gap (colloquially known as the “donut hole”) and provides preventive benefits for Medicare enrollees without cost sharing. The ACA also includes several changes aimed at reducing the growth in Medicare spending. For example, the ACA includes reductions in the growth of Medicare payments to hospitals and other providers, and to Medicare Advantage plans. The law also created an Innovation Center within the Centers for Medicare and Medicaid Services (CMS) tasked with developing and testing new health care payment and delivery models and established the Medicare Shared Savings Program, a permanent accountable care organization (ACO) program in traditional Medicare that offers financial incentives to providers for meeting or exceeding savings targets and quality goals.

Finally, the ACA includes many other provisions that do not relate directly to health coverage. For example, the ACA authorizes the Food and Drug Administration to approve generic versions of biologic drugs. There are also provisions that aim to reduce waste and fraud, expand the health care workforce, increase data collection and reporting on health disparities, and improve public health preparedness.

When passed, the ACA was designed to be budget neutral, with health insurance subsidies and expansions of public programs financed through a variety of taxes and fees on individuals, employers, insurers, and certain businesses in the health sector, as well as savings from the Medicare program. As discussed in more detail below, some of these taxes or fees have since been repealed or reduced to zero dollars, including the individual mandate penalty, the medical device tax, and the so-called “Cadillac Tax,” which would have imposed an excise tax on high-cost employer health plans. Additionally, at times, a tax on health insurance carriers has been temporarily put on hold.

What are the ACA Marketplaces or Exchanges?

Copy link to What are the ACA Marketplaces or Exchanges?

Health Insurance Marketplaces (also known as exchanges) are organizations set up to create more organized and competitive markets for individuals and families buying their own health insurance. The Marketplaces offer a choice of different health plans, certify plans that participate, and provide information and in-person assistance to help consumers understand their options and apply for coverage. Premium and cost-sharing subsidies based on income are available through the Marketplace to make coverage more affordable for individuals and families. People with very low incomes can also find out if they are eligible for coverage through Medicaid and CHIP while shopping on the Marketplace.

Some small businesses can buy coverage for their employees through separate exchanges called Small Business Health Options Program (SHOP) Marketplace plans, but this chapter focuses primarily on the Marketplaces for individuals and families.

There is a health insurance Marketplace in every state for individuals and families and for small businesses. Some enrollment websites are operated by the state government or quasi-governmental bodies at the state level and have a special state name (such as Covered California or The Maryland Health Benefit Exchange). In 28 states where the federal government runs the enrollment website, it is called HealthCare.gov. As of early 2025, three state-based Marketplaces (Arkansas, Illinois, and Oregon) use the federal platform.

The Marketplaces exist alongside other coverage that is also sold to individuals or small businesses. The Marketplaces for individuals and families are part of what is called the “individual insurance market,” which also includes ACA-compliant and non-compliant insurance sold off the Marketplace (also called off-exchange coverage). Similarly, the “small group insurance market” includes the SHOP Marketplace plans as well as other ACA-compliant and non-compliant coverage sold to small businesses.

Who Can Enroll in Individual ACA Marketplace Coverage?

Copy link to Who Can Enroll in Individual ACA Marketplace Coverage?

While many Americans are allowed to purchase unsubsidized coverage on the ACA Marketplaces, these markets primarily exist to fill a gap in coverage options for people who cannot get insurance through work or public programs. Some people who sign up for Marketplace coverage are unemployed or between jobs, while others are students, self-employed or work at businesses that do not offer coverage (e.g., very small companies) or offer coverage that is deemed unaffordable.

To receive the premium tax credit for coverage starting in 2025, a Marketplace enrollee must meet the following criteria:

  • Have a household income at least equal to the Federal Poverty Level (FPL), which for the 2025 benefit year will be determined based on 2024 poverty guidelines.
  • Not have access to affordable coverage through an employer (including a family member’s employer).
  • Not be eligible for coverage through Medicare, Medicaid, or the Children’s Health Insurance Program (CHIP).
  • Have U.S. citizenship or proof of legal residency (lawfully present immigrants whose household income is below 100 percent FPL can also be eligible for tax subsidies through the Marketplace if they meet all other eligibility requirements, though this exception is set to end starting in 2026).
  • If married, must file taxes jointly.

Employer coverage: If a person’s employer offers health coverage but that coverage is deemed unaffordable or of insufficient value, the employee and/or their family may be able to receive subsidies to buy Marketplace coverage. Employer coverage is considered affordable if the required premium contribution is no more than 9.02 percent of household income in 2025. The Marketplace will look at both the required employee contribution for self-only and (if applicable) for family coverage. If the required employee contribution for self-only coverage is affordable, but the required employee contribution for family coverage is more than 9.02 percent of household income, the dependents can purchase subsidized exchange coverage while the employee stays on employer coverage.

The employer’s coverage must also meet a minimum value standard that requires the plan to provide substantial coverage for physician services and for inpatient hospital care with an actuarial value of at least 60 percent (meaning the plan pays for an average of at least 60 percent of all enrollees’ combined health spending, similar to a bronze plan). The plan must also have an annual OOP limit on cost sharing of no more than $9,200 for self-only coverage and $18,400 for family coverage in 2025.

People offered employer-sponsored coverage that fails to meet either the affordability threshold or minimum value requirements can qualify for Marketplace subsidies if they meet the other criteria listed above.

Eligibility for Medicaid: In states that have expanded Medicaid under the ACA, adults with income up to 138 percent FPL are generally eligible for Medicaid and, therefore, are ineligible for Marketplace subsidies. In the states that have not adopted the Medicaid expansion, adults with income as low as 100 percent of FPL can qualify for Marketplace subsidies, but those with lower incomes are not eligible for tax credits and generally not eligible for Medicaid unless they meet other state eligibility criteria.

Starting in 2026, federal policy changes will restrict premium tax credit eligibility for legal immigrants who are ineligible for Medicaid due to their alien status. An exception to the rule restricting tax credit eligibility for adults with income below the FPL was previously made for certain lawfully present immigrants. Other federal rules restrict Medicaid eligibility for lawfully present immigrants, other than pregnant women, refugees, and asylees, until they have resided in the U.S. for at least five years. Prior to the implementation of this policy change, immigrants who would otherwise have been eligible for Medicaid but had not yet completed their five-year waiting period instead qualified for tax credits through the Marketplace. If an individual in this circumstance has an income below 100 percent of FPL, for the purposes of tax credit eligibility, their income would have been treated as though it was equal to the FPL. Immigrants who are not lawfully present are ineligible to enroll in health insurance through the Marketplace, receive tax credits through the Marketplace, or enroll in non-emergency Medicaid and CHIP. In November 2024, the Biden administration published new rules that deemed Deferred Action for Childhood Arrivals (DACA) recipients as lawfully present, making them eligible for subsidized ACA Marketplace coverage. However, finalized Marketplace Integrity and Affordability rules undo this change.

What Services Do ACA Marketplace Plans Cover?

Copy link to What Services Do ACA Marketplace Plans Cover?

The ACA requires all qualified health benefits plans to cover essential health benefits, including those offered through the Marketplaces and those offered in the individual and small group markets off-exchange. Grandfathered individual and employer-sponsored plans (which existed before the ACA was passed) and non-compliant plans (which include short-term plans) do not have to cover essential health benefits.

The law specifies that the essential health benefits package must include at least 10 categories of items and services: ambulatory patient services; emergency services; hospitalization; pregnancy, maternity, and newborn care; mental health and substance use disorder services, including behavioral health treatment; prescription drugs; rehabilitative and habilitative services and devices; laboratory services; preventive and wellness services and chronic disease management; and pediatric services, including oral and vision care. It also requires that the scope of benefits be equal to that of a “typical employer plan.”

These categories are broad and subject to interpretation. For example, there could be limits on the number of physical therapy services an enrollee receives in a year. For more specific guidance on how to interpret these requirements, the federal government allows states to select a “benchmark” health plan (often one that was already offered to small businesses) as a standard.

Essential health benefits are a minimum standard. Plans can offer additional health benefits, like vision, dental, and medical management programs (for example, for weight loss). The ACA prohibits abortion coverage from being required as part of the essential health benefits package. The premium subsidy does not cover non-essential health benefits, meaning that people enrolling in a plan with non-essential benefits may have to pay a portion of the premium for these additional benefits.

Although plans must cover essential health benefits, they are allowed to apply cost sharing (deductibles, copayments, and coinsurance). This means enrollees may still face some out-of-pocket costs when receiving these services. However, preventive health services are required to be covered without cost sharing. Examples of preventive health services include vaccinations, cancer screenings, and birth control.

How Much Do People Pay for Marketplace Plans and How are Subsidies Calculated?

Copy link to How Much Do People Pay for Marketplace Plans and How are Subsidies Calculated?

There are two types of financial assistance available to Marketplace enrollees. The first type, called the premium tax credit (or premium subsidy), reduces enrollees’ monthly payments for insurance coverage. The second type of financial assistance, the cost-sharing reduction (CSR), reduces enrollees’ deductibles and other out-of-pocket costs when they go to the doctor or have a hospital stay. To receive either type of financial assistance, qualifying individuals and families must enroll in a plan offered through a health insurance Marketplace. In addition to the federal subsidies discussed here, some states that operate their own exchange markets offer additional state-funded subsidies that further lower premium payments and/or deductibles or other forms of cost sharing.

Premium Subsidies

Premium tax credits can be applied to Marketplace plans in any of four “metal” levels of coverage: bronze, silver, gold, and platinum. Bronze plans tend to have the lowest premiums but have the highest deductibles and other cost sharing, leaving the enrollee to pay more out-of-pocket when they receive covered health care services, while platinum plans have the highest premiums but very low out-of-pocket costs. There are also catastrophic plans, usually only available to younger enrollees, but the subsidy cannot be used to purchase one of these plans.

The premium tax credit works by limiting the amount an individual must contribute toward the premium for the “benchmark” plan – or the second-lowest cost silver plan available to the individual in their Marketplace. This “required individual contribution” is set on a sliding income scale. In 2025, for individuals with income up to 150 percent FPL, the required contribution is zero, while at an income of 400 percent FPL or above, the required contribution is 8.5 percent of household income. 

Required Individual Contribution to Benchmark Plan Premium for 2025 Coverage Year

These contribution amounts were set by the American Rescue Plan Act (ARPA) in 2021 and temporarily extended by the Inflation Reduction Act (IRA) through the end of 2025. Prior to the ARPA, the required contribution percentages ranged from about two percent of household income for people with income at the FPL to nearly 10 percent for people with income from 300 to 400 percent of FPL. Before the ARPA was passed, people with incomes above 400 percent of FPL were not eligible for premium tax credits. If Congress does not act to extend the IRA enhanced premium tax credits before the end of 2025, they will expire, and the original ACA premium caps will return.

The amount of tax credit is calculated by subtracting the individual’s required contribution from the actual cost of the “benchmark” plan. So, for example, if the benchmark plan costs $6,000 annually, the required contribution for someone with an income of 150 percent FPL is zero, resulting in a premium tax credit of $6,000. If that same person’s income equals 250 percent FPL (or $37,650 in 2025), the individual contribution is four percent of $37,650, or $1,506, resulting in a premium tax credit of $4,494.

The premium tax credit can then be applied toward any other plan sold through the Marketplace (except catastrophic coverage). The amount of the tax credit remains the same, so a person who chooses to purchase a plan that is more expensive than the benchmark plan will have to pay the difference in cost. If a person chooses a less expensive plan, such as the lowest-cost silver plan or a bronze plan, the tax credit will cover a greater share of that plan’s premium and possibly even the entire cost of the premium. When the tax credit exceeds the cost of a plan, it lowers the premium to zero and any remaining tax credit amount is unused.

As mentioned above, the premium tax credit will not apply for certain components of a Marketplace plan premium. First, the tax credit cannot be applied to the portion of a person’s premium attributable to covered benefits that are not essential health benefits (EHB). For example, a plan may offer adult dental benefits, which are currently not included in the definition of EHB. In that case, the person would have to pay the portion of the premium attributable to adult dental benefits without financial assistance. In addition, the ACA requires that premium tax credits may not be applied to the portion of premium attributable to “non-Hyde” abortion benefits. Marketplace plans that cover abortion are required to charge a separate minimum $1 monthly premium to cover the cost of this benefit; this means a consumer who is otherwise eligible for a fully subsidized, zero-premium policy would still need to pay $1 per month for a policy that covers abortion benefits. Finally, if the person smokes cigarettes and is charged a higher premium for smoking, the premium tax credit is not applied to the portion of the premium that is the tobacco surcharge.

Cost-Sharing Reductions

The second form of financial assistance available to Marketplace enrollees is a cost-sharing reduction. Cost-sharing reductions lower enrollees’ out-of-pocket cost due to deductibles, copayments, and coinsurance when they use covered health care services. People who are eligible to receive a premium tax credit and have household incomes from 100 to 250 percent of FPL are eligible for cost-sharing reductions.

Unlike the premium tax credit (which can be applied toward any metal level of coverage), cost-sharing reductions (CSR) are only offered through silver plans. For eligible individuals, cost-sharing reductions are applied to a silver plan, essentially making deductibles and other cost sharing under that plan more similar to that under a gold or platinum plan. Individuals with income between 100 and 250 percent FPL can continue to apply their premium tax credit to any metal level plan, but they can only receive the cost-sharing subsidies if they pick a silver-level plan.

Cost-sharing reductions are determined on a sliding scale based on income. The most generous cost-sharing reductions are available for people with income between 100 and 150 percent FPL. For these enrollees, silver plans that otherwise typically have higher cost sharing are modified to be more similar to a platinum plan by substantially reducing the silver plan deductibles, copays, and other cost sharing. For example, in 2025, the average annual deductible under a silver plan with no cost-sharing reduction is nearly $5,000, while the average annual deductible under a platinum plan is $0. Silver plans with the most generous level of cost-sharing reductions are sometimes called CSR 94 silver plans; these plans have 94 percent actuarial value (which represents the average share of health spending paid by the health plan) compared to 70 percent actuarial value for a silver plan with no cost-sharing reductions.

Somewhat less generous cost-sharing reductions are available for people with income greater than 150 and up to 200 percent FPL. These reduce cost sharing under silver plans to 87 percent actuarial value (CSR 87 plans). In 2025, the average annual deductible under a CSR 87 silver plan was about $700.

For people with income greater than 200 and up to 250 percent FPL, cost-sharing reductions are available to modestly reduce deductibles and copays to 73 percent actuarial value (sometimes called CSR 73 plans). In 2025, the average annual deductible under a CSR 73 silver plan was about $3,600.

Insurers have flexibility in how they set deductibles and copays to achieve the actuarial value under Marketplace plans, including CSR plans, so actual deductibles may vary from these averages. The ACA also requires maximum annual out-of-pocket spending limits on cost sharing under Marketplace plans, with reduced limits for CSR plans. In 2025, the maximum OOP limit is $9,200 for an individual and $18,400 for a family for all QHPs. Lower maximum OOP limits are permitted under cost-sharing reduction plans.

Maximum Annual Limitation on Cost Sharing, 2025

Cost-sharing reductions work differently for Native American and Alaska Native members of federally recognized tribes. For these individuals, cost-sharing reductions are available at higher incomes and can be applied to metal levels other than silver plans.

How Has the ACA Changed Since It Was First Passed?

Copy link to How Has the ACA Changed Since It Was First Passed?

Since it was first signed into law, the ACA has undergone many changes through regulation, legislation, and legal challenges. Some provisions never got off the ground, and others were repealed, while more recent changes have expanded and enhanced other provisions. This section summarizes some of the most significant changes to the law.

Medicaid Expansion: The ACA originally expanded Medicaid to all non-Medicare eligible individuals under age 65 with incomes up to 138% of the FPL. A Supreme Court ruling on the constitutionality of the ACA upheld the Medicaid expansion, but limited the ability of HHS to enforce it, thereby making the decision to expand Medicaid effectively optional for states. As of the beginning of 2025, 40 states and the District of Columbia had expanded Medicaid. Additionally, while not taking up Medicaid expansion under the ACA, Wisconsin did increase Medicaid eligibility to 100% of the FPL, which is where ACA Marketplace subsidy eligibility begins. In the remaining states that have not expanded Medicaid, an estimated 1.4 million people fall into the so-called Medicaid coverage gap, meaning their incomes are too high to qualify for Medicaid but too low to qualify for ACA Marketplace subsidies. The federal government covers 90% of the cost of Medicaid expansion.

Individual Mandate: The ACA also originally included an “individual mandate” or requirement for most people to maintain health insurance. In health insurance systems designed to protect people with pre-existing conditions and guarantee availability of coverage regardless of health status, countervailing measures are also needed to ensure people do not wait until they are sick to sign up for coverage, as doing so would drive up premiums. The ACA included a variety of these countervailing measures, with both “carrots” (e.g., premium tax credits and cost-sharing reductions) and “sticks” (e.g., the individual mandate penalty and limited enrollment opportunities) to encourage healthy as well as sick people to enroll in health insurance coverage.

American citizens and U.S. residents without qualifying health coverage had to pay a tax penalty of the greater of $695 per year up to a maximum of three times that amount ($2,085) per family or 2.5% of household income. The penalty was set to increase annually by the cost-of-living adjustment. Exemptions were granted for financial hardship, religious objections, American Indians, those without coverage for less than three months, undocumented immigrants, incarcerated individuals, those for whom the lowest cost plan option exceeds 8% of an individual’s income, and those with incomes below the tax filing threshold.

Despite the popularity of the ACA’s protections for people with pre-existing conditions, the individual mandate was politically controversial and consistently viewed negatively by a substantial share of the public. In early 2017, under President Trump, the Internal Revenue Service (IRS) stopped enforcing the individual mandate penalty. After several attempts to repeal and replace the ACA stalled out in the summer of 2017, Congress reduced the individual mandate penalty to $0, effective in 2019, as part of tax reform legislation passed in December 2017.

Cost-Sharing Reduction Payments: The ACA originally included two types of payments to insurers participating in the ACA Marketplace. First, insurers received advanced payments of the premium tax credit to subsidize monthly premiums for people buying their own coverage on the Marketplace. Second, insurers were required to reduce cost sharing (i.e., deductibles, copayments, and/or coinsurance) for low-income enrollees and the federal government was required to reimburse insurers for these cost-sharing reductions (CSRs). However, the funds for the payment of cost-sharing reductions were never appropriated. The Trump administration ended federal CSR payments to insurers weeks before ACA Marketplace Open Enrollment for 2018 coverage began. In response to this, most states allowed insurers to compensate for the lack of government payments by raising premiums. At the time, the Congressional Budget Office (CBO) estimated termination of CSR payments to insurers would increase the federal deficit by $194 billion over 10 years, because of these higher premiums and corresponding increased premium tax credit subsidies. Although the CSR payments have ceased, cost-sharing reduction plans continue to be available to low-income Marketplace enrollees.

Enhanced and Expanded ACA Marketplace Premium Tax Credits: Another controversial aspect of the ACA was the so-called “subsidy cliff,” where people with incomes over 400% of the FPL were ineligible for financial assistance on the Marketplace and, therefore, would have to pay a large share of their household income for unsubsidized health coverage. As a result, many middle-income people were being priced out of ACA coverage. The March 2021 COVID-19 relief legislation, the American Rescue Plan Act (ARPA), extended eligibility for ACA health insurance subsidies to people with incomes over 400% of FPL buying their health coverage on the Marketplace. The ARPA also increased the amount of financial assistance for people with lower incomes who were already eligible under the ACA, making many low-income people newly eligible for free or nearly free coverage. Both provisions were temporary, lasting for two years, but the Inflation Reduction Act extends those subsidies through the end of 2025.

Family Glitch: Financial assistance to buy health insurance on the Affordable Care Act (ACA) Marketplaces is primarily available for people who cannot get coverage through a public program or their employer. Some exceptions are made, however, including for people whose employer coverage offer is deemed unaffordable or of insufficient value. For example, people can qualify for ACA Marketplace subsidies if their employer requires them to spend more than about 8-9% (indexed each year) of their household income on the company’s health plan premium. For many years, this affordability threshold was based on the cost of the employee’s self-only coverage, not the premium required to cover any dependents. In other words, an employee whose contribution for self-only coverage was less than the threshold was deemed to have an affordable offer, which means that the employee and their family members were ineligible for financial assistance on the Marketplace, even if the cost of adding dependents to the employer-sponsored plan would far exceed the approximately 8-9% of the family’s income. This definition of “affordable” employer coverage has come to be known as the “family glitch,” which affected an estimated 5.1 million people. Under a Biden administration federal regulation, the worker’s required premium contributions for self-only coverage and for family coverage will be compared to the affordability threshold of approximately 8-9% of household income. If the cost of self-only coverage is affordable, but the cost for family coverage is not, the worker will stay on employer coverage while their family members can apply for subsidized exchange coverage.

Public Opinion: Americans’ views of the Affordable Care Act have evolved over time. From the time the ACA passed, to when the Marketplaces first opened in 2014, and through the months leading up to President Trump’s election in 2016, public opinion of the ACA was strongly divided and often leaned more negative than positive. Many individual provisions of the ACA, such as protections for people with preexisting conditions, were popular, but the individual mandate was particularly unpopular.

News coverage during the ACA Marketplaces’ early years often centered on the rocky rollout, from the early Healthcare.gov website glitches to skyrocketing premiums in subsequent years. Coverage in later years focused on how unprofitable insurers exited the market, leaving people in some counties at risk of having no Marketplace insurer—and thus, no Marketplace through which to access health insurance subsidies.

In 2017, during his first term, President Trump and Republicans in Congress attempted to repeal or fundamentally alter the ACA. As proposals to replace the ACA became more concrete, though, public support for the ACA, particularly among Democrats and Independents, began to grow. Ultimately, the only key aspect of the law that was removed was the penalty for not purchasing health insurance—now lowered to $0 as part of the 2017 tax reform package. Following repeal efforts and the removal of the individual mandate penalty, as well as a stabilization of the ACA Marketplaces, public support for the law has continued to grow and is now solidly more positive than negative. Although this support remains divided by party lines, several Republican-led states have adopted the ACA’s Medicaid expansion through popular votes.

Following repeal efforts and the removal of the individual mandate penalty, as well as a stabilization of the ACA Marketplaces, public support for the law has continued to grow and is now solidly more positive than negative. Although this support remains divided by party lines, several Republican-led states have adopted the ACA’s Medicaid expansion through popular votes.

KFF Health Tracking Poll: The Public's Views on the ACA

How Have the ACA Marketplaces Changed Over Time?

Copy link to How Have the ACA Marketplaces Changed Over Time?

After volatile initial years, the ACA Marketplaces have become more stable—a pattern which can be seen across a variety of measures, including enrollment, premiums and insurer participation.  

Enrollment

Affordable Care Act Marketplace Enrollment (Column Chart)

ACA Marketplace enrollment has more than tripled since its launch in 2014. The number of people who enrolled and effectuated their Marketplace coverage in early 2024 reached 20.8 million, surpassing prior record-setting years in 2021, 2022, and 2023. The recent enrollment growth was likely primarily driven by the enhanced tax credits in the American Rescue Plan Act and the Inflation Reduction Act, as well as the Biden administration’s decision to direct more resources toward marketing, outreach, and enrollment assistance, reversing substantial reductions in funding by the Trump administration.

Individual Market Enrollment Has Reached a Record High of 25.2M People in 2025

The ARPA’s subsidies didn’t simply bring people from off-Marketplace plans to the Marketplace; they also helped increase overall individual market enrollment. Enrollment grew to 25.2 million in early 2025, which is an increase of about 81% from early 2020.

With passage of enhanced tax credits in the American Rescue Plan Act (ARPA), combined with boosted outreach and an extended enrollment period, 2021 marked the first year since 2015 when individual market enrollment increased relative to the year prior. Individual market enrollment grew about 5% from 13.9 million in the first quarter of 2020 to 14.7 million in the first quarter of 2021.

In the early years of the rollout of the ACA Marketplaces, on-exchange enrollment was comparable to off-exchange enrollment, meaning that the Marketplaces represented about half of overall individual market enrollment. Some off-exchange enrollment was represented by people in ACA-compliant coverage (similar to that offered on-exchange, but without subsidies), while other individual market enrollees were signed up for non-compliant coverage, like “grandmothered” or short-term plans.

Non-compliant short-term plans often do not include certain benefits or coverage for pre-existing conditions and can impose a dollar limit on insurance coverage. For example, many short-term plans do not cover maternity care, prescription drugs, or mental health or substance use treatment, and most impose a dollar limit on covered services or drugs. In 2024, the Biden administration finalized a rule that reverses the Trump administration’s expansion of short-term plans.

Premiums

ACA Marketplace premiums have risen substantially over time. When insurers entered the ACA Marketplaces in 2014, most were operating with virtually no experience participating in an individual market like this (e.g., with subsidies, preexisting condition protections, and an individual mandate). Insurers also had to submit premiums almost a year in advance for review and approval by state regulators. Even 2015 premiums were submitted in early 2014, meaning insurers did not have much experience in the market on which to base their premium and claim projections. Eventually, though, it became clear that they were underpriced and unprofitable, so in 2016, many insurers began to raise premiums. By 2017, the temporary reinsurance and risk corridors programs had phased out, leading to another market correction. In 2018, with the discontinuation of cost-sharing reduction payments, insurers raised premiums yet again, though most insurers concentrated these premium increases on silver plans (a practice known as “silver loading”). More recently, though, as the markets have stabilized and as the pandemic led to a temporary reduction in health care utilization, premiums have at times fallen or at least grown at a slower pace. Heading into 2025, ACA Marketplace benchmark premiums rose by about 4% on average, driven primarily by inflation and increased utilization of specialty drugs.

Nationwide Average Lowest Cost Bronze and Benchmark Silver Marketplace Premiums, 2014-2025 (Grouped column chart)

Deductibles and other cost sharing

Generally, deductibles have also risen since the ACA Marketplaces were first launched in 2014. Bronze plans, which typically have the highest deductibles among ACA Marketplace plans, have an average deductible of $7,186 in 2025, compared to $5,113 in 2014. However, as discussed above, many ACA Marketplace enrollees are low income and therefore qualify for cost-sharing reductions if they purchase a silver plan. For the most generous cost-sharing reduction plans, which are available to people with incomes just above the FPL, the average deductible is $87 in 2025, compared to $183 in 2014.  

Average Deductible in ACA Marketplace Plans, 2014-2025 (Line chart)

Insurer participation

Insurer participation in 2025 is more robust than in recent years, surpassing record high levels of participation set in 2023 and 2024.

Insurer participation on the ACA Marketplaces fell dramatically in 2017 with the exit of UnitedHealthcare from most states. In 2018, with President Trump’s announcement that cost-sharing reduction payments would cease and the corresponding attempts to repeal the ACA in Congress, many more insurers exited or scaled back their participation. Though all counties in the country continued to have at least one ACA Marketplace insurer, there had initially been concern that there could have been counties left without any insurer, thus leaving residents in those counties without access to ACA subsidies.

However, in subsequent years, with premium increases and changes in strategies, it became apparent that the ACA Marketplaces could be quite profitable and many insurers entered or expanded their footprints.

Average Number of Issuers Participating in ACA Marketplaces,  Per State, 2014-2025 (Column Chart)

What Does the Federal Government Spend on ACA Subsidies?

Copy link to What Does the Federal Government Spend on ACA Subsidies?

The cost of the ACA subsidies largely depends on how many people enroll and the cost of monthly premiums. The Congressional Budget Office (CBO) expects the number of people with subsidized Marketplace coverage to continue to grow through 2025, but then drop after if the Inflation Reduction Act tax credits expire that year.

From 2025-2034, CBO expects the cost of federal Marketplace subsidies and related programs to total $1.32 trillion, ranging from $118 billion to $147 billion per year. This includes an estimated $966 billion in direct spending on ACA Marketplace subsidies, $177 billion on the Basic Health Program and 1332 waivers, as well as $176 billion in revenue reductions over ten years. These estimates, however, do not account for federal policy changes that were finalized in summer 2025 as part of the budget reconciliation legislation and finalized Marketplace Program Integrity and Affordability rule.

Future Outlook

Copy link to Future Outlook

The ACA has faced both support and opposition over time, and its fate has been subject to numerous political and legal debates, including efforts to repeal and replace the law and to overturn it in whole or in part in several court cases. Future changes in presidential administrations and shifts in the composition of Congress will likely continue to impact the implementation and stability of the ACA.

Key issues to watch include:

Federal Policy Changes: Federal policy changes finalized and passed in the summer of 2025 will change how the ACA Marketplaces will operate in the coming years. Combined, the finalized Marketplace Integrity and Affordability final rule as well as the budget reconciliation legislation will make several changes to consumer protections, ACA Marketplace coverage and premium tax credit eligibility, as well as verification processes. Implementation dates of specific policies vary, but some are set to begin in August of 2025. Changes include effectively ending auto-renewals, removing repayment limits on the premium tax credit, and implementing new eligibility verification procedures.  The CBO estimates that an additional  10 million people would become uninsured due to the impact of the budget reconciliation legislation, with about 2 million becoming uninsured due to changes to the ACA Marketplaces.

Enhanced Premium Tax Credits: Currently, the enhanced premium tax credits in the ACA Marketplaces are set to expire at the end of 2025. If these tax credits are allowed to expire, people purchasing subsidized coverage will face significant increases in their monthly premium payments and some may become priced out of the market. Some action has been taken ahead of a potential expiration. In preparation for the possibility of enhanced tax credits expiring, some states are working on ways to fund state subsidies that keep the cost of ACA Marketplace coverage affordable. The CBO previously projected that an additional 4.2 million people would become uninsured by 2034 if the enhanced premium tax credits expire.

State Actions: In recent years, some states have moved off the federal platform (Healthcare.gov) to implement their own enrollment websites. Additionally, more states have expanded Medicaid. Some states have sought 1332 waivers under the ACA to implement reinsurance programs, expand coverage to undocumented residents (though federal policy changes discussed above will undo these efforts), and create public options.

Consumer Protections: The ACA includes various consumer protections that continue to evolve through the regulatory process. For example, proposed and finalized rulemaking has focused on improving network adequacy, simplifying the shopping process, and reexamining essential health benefits. Planned federal policy changes will undo some of the consumer protection processes currently in place. In response to claims of mass fraudulent enrollment, the finalized Marketplace Integrity and Affordability Rule was issued in June 2025. In it, CMS issued rules permitting coverage denials for outstanding premium payments from prior coverage and eliminated the automatic 60-day extension to resolve income discrepancies.

Funding Cuts: In February 2025, CMS announced that it would be reducing funding for its navigator program down from $100 million to $10 million starting next year. This is equal tothe amount awarded to navigators in 2018-2020 during President Trump’s first administration.

Health Costs and Affordability: Though the ACA has made insurance coverage more accessible and affordable for millions of people, health costs in the United States continue to be high and many people with insurance nonetheless face cost-related barriers to care.

Resources

Copy link to Resources

Citation

Copy link to Citation

Ortaliza, J., McGough, M., & Cox, C., The Affordable Care Act 101. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-the-affordable-care-act/ (date accessed).

Health Care Costs and Affordability

KFF Authors:

Table of Contents

Introduction

Copy link to Introduction

Health care costs in the United States generally grow faster than inflation. The U.S. far exceeds other large and wealthy nations in per capita health spending, and health care represents a much larger share of the economy in the U.S. than in peer nations. Despite substantial spending, the U.S. health system grapples with disparities and gaps in coverage. Elevated health care expenditure in the U.S. does not consistently translate into superior health outcomes. Rising health care costs instead contribute to Americans facing difficulties affording medical care and drugs, even among those with insurance.

How Has U.S. Health Care Spending Changed Over Time?

Copy link to How Has U.S. Health Care Spending Changed Over Time?

Many people are familiar with the high and rising cost of health care in the United States from seeing how much they spend on their own health insurance premiums and out-of-pocket costs. In addition to these very visible health costs, there are also tax dollars that go to fund public programs and the amounts employers spend toward their employees’ health insurance premiums. Total national health expenditures include spending by both public programs and private health plans, as well as out-of-pocket health spending. Total health expenditures represent the amount spent on health care (such as doctor visits, hospital stays, and prescription drugs) and related activities (such as insurer overhead and profits, health research and infrastructure, and public health).

Total Health Spending Reached $4.9 Trillion in 2022

Total National Health Expenditures, US dollars, 1970-2023

Health spending in the U.S. has risen sharply over the last several decades. The official data on national health expenditures from the Centers for Medicare and Medicaid Services (CMS) show health spending totaled $74.1 billion in 1970. By 2000, health expenditures had reached about $1.4 trillion, and in 2023 the amount spent on health had more than tripled to $4.9 trillion. In the first year of the COVID-19 pandemic, health spending accelerated by 10.4% from 2019 to 2020, even as the use of health care dropped, driven largely by public health spending and financial relief provided to health care providers. Most recently, health spending grew 7.5% from 2022 to 2023, faster than the previous year’s 4.6% increase from 2021 to 2022. Health spending is expected to continue to grow at a similar pace for the foreseeable future.

In the chart above, spending is shown in terms of both nominal dollar values (not inflation-adjusted) and constant 2023 dollars (inflation-adjusted based on the personal consumption expenditures, or PCE, index). Inflation in the health sector increased slightly faster than across the general economy in 2023.

Currently, health care represents about 18% of the U.S. economy (measured as a share of gross domestic product, or GDP). In other words, almost 1 out of every 5 dollars spent in the U.S. goes toward health care. Back in 1960, health spending represented just 5% of GDP, meaning 1 in every 20 dollars in the U.S. economy was spent on health care. 

Per Capita Out-of-Pocket Expenditures, 1970-2023

Out-of-pocket costs have also risen over time. Out-of-pocket costs represent the amount of money spent by individuals on health care that is not paid for by a health insurance plan or public program like Medicare or Medicaid. This includes cost-sharing, the most common forms of which are deductibles (an amount that must be paid before most services are covered by the plan), copayments (fixed dollar amounts), and coinsurance (a percentage of the charge for services). (i.e., copays, deductibles, coinsurance), as well as health spending by uninsured people or spending by insured people for care that is not covered at all by health insurance. Out-of-pocket spending does not include the amount spent on a person’s monthly health insurance premium.

Out-of-pocket spending per person was $115 in 1970 (or, adjusted for inflation, $703). By 2023, out-of-pocket spending had reached $1,514 per person. Despite this rise in out-of-pocket spending, health insurance now covers a larger share of total health spending (73%) than it did in 1970 (27%), in part because more people have gained coverage, especially public coverage, but also because health insurance spending per enrollee has grown.

What Factors Contribute to U.S. Health Care Spending?

Copy link to What Factors Contribute to U.S. Health Care Spending?

Over the last several decades, health spending has been driven higher by a number of factors, including but not limited to an aging population, rising rates of chronic conditions, advancements in medicine and new technologies, higher prices, and expansions of health insurance coverage. While there are always differences across countries, many of these factors driving health costs upward in the U.S. are also driving health costs growth in peer nations. For example, while the U.S. population is indeed aging and that is driving health costs up, many large and wealthy nations have even more rapidly aging populations.

Other factors may explain the United States' relatively high health spending compared to its peers. The U.S. health system is fragmented, with many private and public payers, and with regulation of these payers split between states and the federal government. However, these features are not entirely unique to the U.S., either. Indeed, some other countries with much lower health spending have multiple private payers or differences in public programs across states or provinces.  The U.S. is also not alone in having a mainly fee-for-service payment system.

The U.S. health insurance system is largely voluntary, whereas peer countries’ health systems are almost entirely compulsory. Additionally, the U.S. federal and state governments have generally done less to directly regulate or negotiate prices paid for medical services or prescription drugs than have governments of similarly large and wealthy nations. The U.S. often pays higher prices for the same brand-name prescription drugs, hospital procedures, and physician care than similarly large and wealthy countries do.

There are other factors, largely outside the control of the health system that are also likely at play, such as socioeconomic conditions (like income inequality and other social determinants of health), and differences in so-called lifestyle factors (like diet, drug use, or physical activity) that could contribute both to higher spending and worse outcomes.

Breaking total national health spending into its components can reveal the major drivers of health costs and where cost containment efforts could be most effective. The charts below show various ways of examining the key contributors to health spending. For example, the National Health Expenditure Accounts show trends in how health spending varies by type of service (e.g., hospital care vs. retail prescription drugs) or by source of funds (e.g., private health plans vs. public programs). An alternative and relatively new approach to understanding health spending is to break out total health spending into the share that goes to treat certain diseases (e.g., heart disease, cancer). Finally, health spending can also be better understood by looking at trends in prices (e.g., the dollar amount for a hospital stay) and utilization (e.g., the number of hospital stays). 

Hospital and Physician Services Represent Half of Total Health Spending

Relative Contributions to Total National Health Expenditures, by Service Type, 2023

Most health spending in the U.S. and in peer countries is on hospital and physician care, followed by prescription drugs. In the U.S., hospital spending represented close to a third (31.2%) of overall health spending in 2023, and physicians/clinics represented 20.1% of total spending. In comparison to other large and wealthy countries, the U.S.’s higher spending on inpatient and outpatient care explains the vast majority of higher spending on health care overall.

Spending Has Grown for Hospitals, Physicians, and Drugs

Average Annual Expenditures Growth Rate for Select Service Types, 1970-2023 (Grouped column chart)

During the 1970s, growth in hospital expenditures outpaced other services, while prescriptions and physician and clinic services saw faster spending growth during the 1980s and 1990s. From 2020 to 2023, retail prescription drugs experienced the fastest growth in spending at 8.6%, following 3.3% average annual growth from 2010 to 2020. Average spending growth for hospitals and physicians/clinics between 2020 and 2022 was 6.2% and 6.3%, respectively.

On a Per-Enrollee Basis, Private Insurance Spending Has Typically Grown Much Faster Than Medicare and Medicaid Spending

Cumulative Growth in Per-Enrollee Spending by Private Insurance, Medicare, and Medicaid, 2008-2023

Per enrollee spending by private insurance grew by 80.4% from 2008 to 2023 – much faster than both Medicare and Medicaid spending growth per enrollee (50.3% and 30.3%, respectively). Private insurance often pays higher prices for health care compared to prices paid by Medicare and Medicaid.

Per enrollee spending by Medicaid rose by 7.9% in 2023 from the previous year, and also continued to increase in private insurance and Medicare (5.9% and 7.1% respectively). Medicare and private insurance per-enrollee spending continued to grow faster between 2021 and 2023 after slower growth in 2020. Medicaid per-enrollee spending had previously declined in 2021 as total enrollment grew, particularly among children and non-elderly adults, who generally have lower per-enrollee spending.

A Substantial Share of Health Spending Goes Toward the Treatment of Circulatory and Musculoskeletal Conditions

Distribution of total medical services expenditures (US $ billions), by medical condition, 2021

An alternative way of examining the components of health spending is to use the Bureau of Economic Analysis (BEA)’s Health Care Satellite Account, which estimates spending and price growth by disease category (e.g., cancer, infectious disease). This approach differs from the official categorization of health spending by service type (e.g., provider services). Essentially, the new satellite account redefines the “commodity” in healthcare as the treatment for specific diseases, rather than a hospital stay or a physician visit. BEA researchers found that the largest categories of medical services spending include the treatment of circulatory diseases (10.4% of health spending in 2021), musculoskeletal conditions (9.4%) and infectious diseases (9%). Another large share of health spending (15.1%) is for “ill-defined conditions,” which can include routine check-ups and follow-up care that is not easily designated for a particular illness.

Health Spending is a Function of Prices and Use

Annual Percent Change in Price and Quantity Personal Consumption Expenditure Indexes of Health Services, 1970-2025 (Line chart)

Health services spending is generally a function of prices (e.g., the dollar amount charged for a hospital stay) and utilization (e.g., the number of hospital stays).

People and health plans in the U.S. often pay higher prices for the same prescription drugs or hospital procedures than people in other large and wealthy nations do. In terms of utilization, there is not much evidence that people in the U.S. use more health care. In fact, Americans generally have shorter average hospital stays and fewer physician visits per capita. Therefore, a large part of the difference in health spending between the U.S. and its peers can be explained by higher prices, more so than higher utilization.

Over time, within the U.S., prices and utilization have driven health cost growth to varying degrees. In the 1980s and early 1990s, growth in health care prices far exceeded growth in use. Faster growth in health prices in the U.S. during this time drove the divergence in per capita health spending between the U.S. and other large, wealthy OECD countries. While health care prices have grown more moderately in recent decades, prices in the U.S. for health services continue to exceed what other countries pay.

More recently, the COVID-19 pandemic led to fluctuations in health care use. Early in the pandemic, many health services, such as elective surgeries, were postponed or cancelled and many elected to not get care to avoid infections at health care sites. In 2021, health services use increased by 9% from the previous year, but subsequent years showed slightly lower growth rates (2024 health services use increased 5.6% from 2023). This increase in health care use in 2021 followed a sharp decrease in health utilization in 2020. Health care prices increased moderately – between 2 and 3% - between 2020 and 2024, but changing market conditions since the pandemic and policies enacted in 2025 are likely to increase health costs at an increasing rate.

How Does Health Care Spending Vary Across the Population?

Copy link to How Does Health Care Spending Vary Across the Population?

A small portion of the population accounts for a large share of health spending in a given year. Although we tend to focus on averages, a small number of people spend around the average since individual health needs vary over the life course. Some portions of the population (older adults and those with serious or chronic illnesses) require more and higher-cost health services than those who are younger, healthier, or otherwise in need of fewer or less costly services.

Older People and People with Significant Health Needs Account for Most Health Expenditures

Share of Total Population and Total Health Spending, by Age Group and Health Status, 2022

While there are people with high spending at all ages, overall, people 55 and over accounted for 54% of total health spending in 2022, despite making up only 31% of the population. In contrast, people under age 35 made up 44% of the population but were responsible for only 23% of spending.

People with significant health needs account for a large portion of total health spending. People reporting fair or poor health status account for 11% of the population and 27% of the total health spending.

A Small Share of the Population Incurs Most of Health Spending

Share of Total and Out-of-Pocket Health Spending, by Percentile, 2022

In 2022, the top 5% of people with the highest health spending accounted for half of total health spending and had an average of $67,300 in health expenditures annually; people with health spending in the top 1% have average spending of over $147,000 per year. At the other end of the spectrum, the 50% of the population with total health spending below or equal to the 50th percentile accounted for only 3% of all health spending; the average spending for this group was $374.

Out-of-pocket spending on health services is concentrated similarly to overall health spending. In this chart, out-of-pocket spending includes direct payments to providers and cost-sharing, including deductibles, copays, and coinsurance, but does not include monthly premium payments or contributions towards health coverage. Out-of-pocket health spending is similarly concentrated among high-health-need individuals. A small portion of the population accounts for a substantial share of total out-of-pocket health spending in a year.

In 2022, people in the top 1% of out-of-pocket spending paid about $23,700 out-of-pocket for health services on average per year, and people in the top 10% spent an average of $6,126 out-of-pocket per year. People who are in the bottom 50% of out-of-pocket spending spent an average of $24 out of pocket.

How Do High Health Costs Affect Affordability of Care?

Copy link to How Do High Health Costs Affect Affordability of Care?

In addition to being expensive for the nation as a whole, health care is often also expensive for individuals. High health costs can particularly pose a hardship for people who are in worse health and those with lower incomes. However, challenges affording health care are not limited to certain groups; these challenges are pervasive across the U.S. Even people with private health insurance through their employers are often exposed to high and rising deductibles, and therefore also face affordability challenges. A substantial share of the population does not have enough savings or other liquid assets to afford a high deductible or out-of-pocket maximum common in private health plans.

When health care is unaffordable, it can lead to cost-related access barriers, like forgoing or delaying needed medical care. For those who still receive unaffordable health care, this care can lead to medical debt and other forms of financial instability. Some people experience both types of affordability challenges, missing some needed care while also incurring medical debt for other care.

Half of Adults Say it is Difficult to Afford Health Care Costs

Nearly Half of Adults Say It Is Difficult To Afford Health Care Costs, Including Large Shares of the Uninsured, Black and Hispanic Adults, and Those With Lower Incomes

Almost half of U.S. adults say it is difficult to afford health care costs, and one in four say they or a family member in their household had problems paying for health care in the past 12 months. Younger adults, those with lower incomes, adults in fair or poor health, and the uninsured are particularly likely to report problems affording health care in the past year.

Among those under age 65, uninsured adults are more likely to say affording health care costs is difficult (82%) compared to those with health insurance coverage (44%).

Those who are covered by health insurance are not immune to the burden of health care costs. About 4 in 10 insured adults worry about affording their monthly health insurance premium, and 62% worry about affording their deductible before health insurance kicks in. Indeed, large shares of adults with employer-sponsored insurance (ESI) and those with Marketplace coverage rate their insurance as “fair” or “poor” when it comes to their monthly premium and out-of-pocket costs to see a doctor.

1 in 3 Adults Report Putting Off Health Care Because of Cost

Three in Four Uninsured Adults Say They Have Skipped or Postponed Getting Health Care They Needed in the Past 12 Months Due to Cost (Table)

Cost-related barriers to accessing health care are more common for some demographic groups than others. For example, people who are Hispanic, lower-income, in worse health, and/or uninsured tend to have higher rates of self-reported cost-related access barriers.

One-quarter of adults say that in the past 12 months they have skipped or postponed getting health care they needed because of the cost, according to KFF polling. Women are more likely than men to say they have skipped or postponed getting health care they needed because of the cost (38% vs. 32%). Adults ages 65 and older, most of whom are eligible for health care coverage through Medicare, are much less likely than younger age groups to say they have not gotten health care they needed because of cost. Three in four uninsured adults (75%) say they have skipped or postponed getting health care they needed due to cost. Insured people are not immune from cost-related barriers to accessing care and more than one in three adults with insurance (37%) report not getting health care they needed due to cost.

What Impact Do Health Care Costs Have on Financial Vulnerability?

Copy link to What Impact Do Health Care Costs Have on Financial Vulnerability?

Despite the vast majority of the United States population having health insurance, medical debt is not uncommon. Different ways of measuring medical debt result in different estimates of prevalence, but regardless of the method, there is consensus that medical debt is a persistent and pervasive problem in the United States, including for people with insurance.

One way to examine medical debt is through credit reporting, but medical debt is often disguised as other forms of debt when people pay for medical bills on their credit cards or choose to pay off their medical bills while falling behind on other payments.

Another way to measure medical debt is with surveys, which can allow respondents to describe their debt with more detail or nuance. Questions about medical debt and other financial matters can be difficult to compare across surveys. For example, it is not always clear whether respondents are answering about their personal experiences or about their broader family or household. Surveys may also differ in the way they define medical debt or describe what forms of debt to include. 

The KFF Health Care Debt Survey asked respondents to think about money that they currently owe for their own health or dental care or someone else’s, such as a family member or dependent. The KFF Health Care Debt Survey finds that 41% of adults currently have some form of debt caused by their own or a family member’s medical or dental bills.

Four In Ten Adults Currently Have Debt Due to Medical or Dental Bills (Table)

The  U.S. Survey of Income and Program Participation (SIPP)  asks whether money was owed for a medical bill and not paid in full during the past year for each person in the sample household. SIPP results, therefore, can be looked at on the individual level or for an overall household. This survey shows that about 1 in 12 adults have medical debt they owe for themselves or their family’s medical care in the past year.

Regardless of the survey used to examine medical debt, common themes emerge when looking at differences across demographic groups: adults who are Black, uninsured, lower-income, and in worse health are more likely to have medical debt. People with incomes under $40,000 are significantly more likely than people with higher incomes to go into debt to cover an unexpected medical bill, and people with disabilities are also much more likely to have significant medical debt, which, in addition to the burden of medical costs, could also reflect inadequate supplemental income for people who are unable to work due to disability or illness.

Nationally, Medical Debt Totals at Least $200 Billion

Share of Aggregate Total Medical Debt in the U.S., by the Amount of Debt Individuals Owe, 2023

The Consumer Financial Protection Bureau (CFPB) estimates that $88 billion in medical debt is reflected on Americans’ credit reports. However, credit reports may not capture all forms of medical debt. For example, medical debt disguised as credit card debt or money owed to family or friends may not be captured. Surveys may capture medical debt that is not visible on credit reports or is otherwise disguised as another form of debt. The 2023 Survey of Income and Program Participation suggests that total medical debt owed was at least $200 billion at the end of 2023.

Medical Debt is Associated with Financial Vulnerability Across a Range of Indicators

Medical Debt is Associated with Other Forms of Financial Vulnerability (Split Bars)

The National Financial Capability Survey (NFCS) is a triennial survey sponsored by the FINRA Foundation that provides information on the financial security, experiences, and vulnerabilities of people and households.

People with medical debt are much more likely to have other forms of financial distress than those without medical debt. Indicators of financial vulnerability — such as spending more money than one’s income, having no “rainy day” fund, or agreeing with the statement “I am just getting by financially” — are more common among adults with medical debt than those without. Additionally, people with medical debt are more likely to overdraw their checking account, have a credit card balance that exposes them to interest payments, take a cash advance on their credit card, or have been contacted by debt collectors. Adults with medical debt are much more likely to use payday loans or other costly loans than those without medical debt.

How Much is Health Care Spending Expected to Grow?

Copy link to How Much is Health Care Spending Expected to Grow?

Each year, actuaries from the Centers for Medicare and Medicaid Services (CMS) project future spending on health. With health care utilization returning to pre-pandemic levels and price inflation in the health sector continuing to outpace general economic inflation, per-person health spending increased 7% in 2023. Annual per capita health spending is projected to grow at an annual rate of 5% per capita on average from 2023 to 2032.

Health Spending as a Percent of Gross Domestic Product (GDP), Actual (2015 - 2023) and Projected (2024 - 2032)

An aging population, labor pressure driving higher prices, and new high-cost prescription drugs coming to market are expected to contribute to a growth in health spending. Health spending was 17.6% of the U.S. economy in 2023 and is expected to reach 19.7% by 2032.

The pandemic has had direct and indirect effects on the health system that can make projections difficult. COVID-19 has led to new costs for vaccination, testing, and treatment and has also caused other shifts in health utilization and spending. Some people avoided medical settings out of concern of contracting COVID and thus missed or delayed routine care or cancer screenings earlier in the pandemic, for example, which could lead to pent-up demand, worsening health conditions, or more complex disease management going forward. Increased use of telemedicine could also shift spending patterns in the future. Further, the recent broad-based inflation trends in the economy and health sector employment trends also add to the uncertainty of these projections.

Federal Government Infusion of Public Health Funding Has Subsided Since Early in the COVID-19 Pandemic

Federal and State/Local Expenditures on Public Health, US$ Billions, 1970-2023

Total national health spending includes spending on direct patient care, as well as spending on public health or prevention. After a sharp increase in federal funding in 2020 driven by the national response to the COVID-19 pandemic, spending on public health has fallen, decreasing by over 58% between 2022 and 2023. Meanwhile, state and local public health spending grew 5%, in line with previous years. Overall public health spending is expected to continue to decline over the next couple of years.

Future Outlook

Copy link to Future Outlook

Signed in July 2025, the tax and budget reconciliation law (formerly known as the “One Big Beautiful Bill Act”) includes provisions for addressing federal spending on Medicaid and Affordable Care Act exchanges. The Congressional Budget Office (CBO) expects the law to decrease spending on Medicaid and the Affordable Care Act (ACA) Marketplaces by over $1 trillion and lead to 10 million more uninsured people through 2034.

Additional policy issues that will shape future health spending and affordability include:

  • Evolution of State Cost Controls: States implementing measures to control health cost growth, including those potentially supported by the Biden Administration’s new AHEAD model, may prompt further experimentation; however, states can only regulate a subset of private health insurance plans.
  • Price Transparency Requirements: Federal price transparency requirements aim to illuminate prices paid to hospitals and providers. There remain challenges with the quality of the data, though CMS continues to request suggestions for improved guidelines. As for a budgetary impact, CBO predicted minimal impact on health sector prices.
  • Prescription Drug Pricing: The Trump administration’s 2025 executive order called on pharmaceutical manufacturers to match most-favored-nation prices (MFN, the lowest price offered in other developed nations). The effects of this order on prescription drug prices in the U.S. remain uncertain. Additionally, the Inflation Reduction Act of 2022, targeting Medicare drug spending through government negotiation of drug prices, is expected to reduce Medicare costs, but potential far-reaching effects are still unclear. While CBO expects minimal effects on the availability of new treatments, there is considerable uncertainty surrounding those estimates.
  • Expansion of Virtual Care: The COVID-19-induced rise in telehealth, with expanded reimbursement and access, has uncertain impacts on care coordination, quality, health outcomes, and costs.
  • Market Dynamics and Anticompetitive Practices: Consolidation among providers, insurers, and drug manufacturers has elevated health care prices, leading to regulatory actions against anticompetitive practices, aiming to protect consumers from rising costs.
  • Provider Payment Reforms: Bipartisan efforts in site-neutral payment reform, addressing concerns about higher payments in outpatient settings, have led to Medicare implementing site-neutral payments in some settings and additional legislative proposals. However, challenges in provider charging practices and facility fees persist.
  • Value-Based Payment Models: The proliferation of value-based care aims to transfer some of the cost risks from payers to providers, but concerns remain about the effectiveness of these approaches, limited quality improvement, administrative burdens, and reduced physician participation incentives. 
  • Changes in Coverage: Despite reduced uninsured rates through continuous Medicaid enrollment and expanded Affordable Care Act Marketplace subsidies during the pandemic, affordability challenges persist among the insured. Renewed disenrollments from Medicaid and the expiration of Marketplace subsidies after 2025 may increase uninsured rates and affordability issues.
  • Addressing Medical Debt: Ongoing efforts to address medical debt involve buying medical debt for forgiveness and regulatory actions. However, the root causes of high health costs and underinsurance remain untouched by most efforts to mitigate the negative effects of medical debt.

Resources

Copy link to Resources

Citation

Copy link to Citation

Amin, K., Cox, C., Ortaliza, J. & Wager, E., Health Care Costs and Affordability. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-health-care-costs-and-affordability/ (date accessed).

The Uninsured Population and Health Coverage

Table of Contents

Introduction

Copy link to Introduction

Health coverage in the United States is marked by a blend of private and public insurance options that leaves about 8% of the population uninsured. This coverage system has evolved over the years, most recently with the implementation of the Affordable Care Act (ACA), which aimed to reduce the uninsured rate by expanding Medicaid, creating health insurance Marketplaces for individuals, and providing subsidies to make the coverage more affordable. Many factors, including economic conditions, federal and state policy changes, and significant health crises, such as the COVID-19 pandemic, influence the uninsured rate. The ACA and policy changes designed to protect coverage during the pandemic led to increased health coverage overall; however, passage of the 2025 Federal Budget Reconciliation Bill (referred to as the One Big Beautiful Bill Act) along with other policy changes are expected to increase significantly the number of people who are uninsured over the next ten years.

What is the Landscape of Health Care Coverage in the United States?

Copy link to What is the Landscape of Health Care Coverage in the United States?

Health coverage in the U.S. is a complex patchwork of private and public insurance coverage options. In 2023, most residents had private insurance coverage, with nearly half covered by an employer-based plan. About 1 in 5 U.S. residents received coverage through the Medicaid program, the federal and state-financed comprehensive health coverage program for low-income people. Another roughly 15% of the population had health coverage from the federal Medicare program, which covers seniors and people under age 65 with long-term disabilities. About 6% of the population had private non-group insurance either purchased through the ACA Marketplace or off-market, and just over 1% of the population was covered through the military’s TRICARE or VA health care programs. The uninsured rate for the total population was 7.9% for the year (Figure 1). (In some cases, people have multiple forms of coverage. For example, about 12 million people are enrolled in both Medicare and Medicaid and are classified in these figures as covered by Medicaid.)

Health Insurance Coverage of the Total Population, 2023

Trends in the Uninsured Rate

Copy link to Trends in the Uninsured Rate

In 2023, there were 25.3 million uninsured residents ages 0-64, and the uninsured rate among the population ages 0-64 was 9.5%, the lowest rate in U.S. history (Figure 2). The analysis of the uninsured population focuses on coverage among people ages 0-64 since Medicare offers near-universal coverage for seniors—just 457,000, or less than 1%, of people over age 65 were uninsured.

 Uninsured Rate of People Ages 0-64, 2010-2023

Prior to the implementation of the ACA, gaps in the public insurance system and lack of access to affordable private coverage left over 40 million people without health insurance. The ACA expanded Medicaid coverage to nearly all adults with incomes up to 138% of the federal poverty level (FPL) (the poverty level in the continental U.S. is $15,650 for a single individual in 2025) and created new health insurance Marketplaces through which individuals can purchase coverage with financial help to afford premiums and cost-sharing. Following the passage of the ACA in 2010 and the rollout of the coverage provisions, the number of uninsured people ages 0-64 dropped to 27 million in 2016. The ACA envisioned that all states would adopt the Medicaid expansion; however, a Supreme Court ruling in 2012 made expansion optional for states. As of early 2025, 40 states and Washington, D.C. had adopted the ACA’s Medicaid expansion (Figure 3).

Status of State Action on the Medicaid Expansion Decision (Choropleth map)

The declines in uninsured rates following implementation of the ACA coverage expansions were largest among poor and near-poor individuals, particularly adults. People of color, who had higher uninsured rates than White people prior to 2014, had larger coverage gains from 2013 to 2016 than White people, although the coverage disparities were not eliminated.

Before implementation of the ACA, expansions of Medicaid coverage and the enactment of the Children’s Health Insurance Program (CHIP) helped to lower the uninsured rate for children. Changes in the 1980s and early 1990s expanded Medicaid eligibility levels for children and pregnant people, and the establishment of CHIP in 1997 provided coverage for children with incomes above Medicaid thresholds. When states implemented CHIP, extensive outreach efforts along with the adoption of streamlined processes facilitated enrollment of children in Medicaid and CHIP and reduced the number of uninsured children.

After declining through 2016, the number of uninsured people and the uninsured rate began increasing in 2017 and continued to grow through 2019. Generally favorable economic conditions as well as policy changes during the Trump Administration, such as reduced funding for outreach and enrollment assistance, encouraging periodic Medicaid eligibility checks, changes to immigration policy related to public charge rules, and approval of some demonstration waivers to restrict enrollment led to a decline in Medicaid enrollment, which likely contributed to the increase in uninsured people.  

With the arrival of the COVID-19 pandemic, policies adopted to protect coverage drove a decline in the uninsured population from 2019 to 2023. The Families First Coronavirus Response Act required states to keep people continuously enrolled in Medicaid in exchange for enhanced federal funding. Medicaid continuous enrollment ended in March 2023, and most states completed renewals for individuals who enrolled during continuous enrollment by December 2024. In addition, the American Rescue Plan Act (ARPA) provided temporary enhanced ACA Marketplace subsidies to make Marketplace coverage more affordable, and these subsidies were renewed for another three years in the Inflation Reduction Act of 2022. These enhanced subsidies will expire at the end of December 2025 unless Congress acts to extend them.

Who is Uninsured in the United States?

Copy link to Who is Uninsured in the United States?

Most people who are uninsured are adults under age 65, are in working low-income families, are people of color, and, reflecting geographic variation in income, immigration status, and the availability of public coverage, live in the South or West. In 2023, over 8 in 10 people ages 0-64 who were uninsured were adults and 16% were children.

Nearly three-quarters (73.7%) of the uninsured population ages 0-64 had at least one full-time worker in their family and an additional 11.2% had a part-time worker in their family (Figure 4). More than 8 in 10 (80.9%) people ages 0-64 who were uninsured were in families with incomes below 400% FPL in 2023 and nearly half (46.7%) had incomes below 200% FPL. People of color comprised 62.9% of the uninsured population ages 0-64 in 2023 despite making up about 46% of residents ages 0-64. Most uninsured individuals (74.2%) were U.S. citizens, while 25.8% were noncitizens in 2023. Nearly three-quarters lived in the South and West.

Family Work Status of Uninsured People Ages 0-64, 2023

Adults ages 19 to 64 are more likely to be uninsured than children. The uninsured rate among children (5.3%) was less than half the rate among adults ages 19-64 (11.1%) in 2023, largely due to the broader availability of Medicaid and CHIP coverage for children than for adults. Among adults ages 19-64, men had higher uninsured rates than women in 2023 (12.6% vs. 9.5%).

Reflecting persistent disparities in coverage, people of color are generally more likely to be uninsured than White people. In 2023, American Indian and Alaskan Native (AIAN) and Hispanic people ages 0-64 had the highest uninsured rates at 18.7% and 17.9%, respectively, which were nearly three times higher than the uninsured rate for White people (6.5%). Uninsured rates for Native Hawaiian or Pacific Islander (NHPI) (12.8%) and Black people (9.7%) ages 0-64 were also higher than the rate for their White counterparts (Figure 5). These differences in uninsured rates are driven by lower rates of private coverage among these groups. Medicaid coverage helps to narrow these differences but does not fully offset them.

Uninsured Rates among the Population Ages 0-64 by Selected Characteristics, 2023 (Bar Chart)

Noncitizens are more likely than citizens to be uninsured. Nearly one-third of noncitizen immigrants were uninsured in 2023 while the uninsured rate for U.S.-born citizens was 7.5% and 8.9% for naturalized citizens. One in 4 children has an immigrant parent, including over 1 in 10 (12%) who are citizen children with at least one noncitizen parent.

Uninsured rates vary by state and by region and were generally higher in states that had not taken up the ACA Medicaid expansion in 2023 (Figure 6). Economic conditions, availability of employer-sponsored coverage, and demographics are other factors contributing to variation in uninsured rates across states.

Uninsured Rates Among Population Ages 0-64 by State, 2023

Why are People Uninsured?

Copy link to Why are People Uninsured?

The fragmented U.S. health coverage system leads to gaps in coverage. While employer-based insurance is the prevalent source of coverage for the population ages 0-64, not all workers are offered coverage by their employer or, if offered, can afford their share of the premiums. Medicaid covers many low-income individuals, especially children, but eligibility for adults remains limited in most states that have not adopted the ACA Medicaid expansion. While subsidies for Marketplace coverage are available for many low and moderate-income people, few people can afford to purchase private coverage without financial assistance.

The cost of health coverage and care poses a challenge for the country broadly and is a significant barrier to coverage for people who are uninsured. In 2023, 63.2% of uninsured adults ages 18-64 said they were uninsured because coverage is not affordable, making it the most common reason cited for being uninsured (Figure 7). Other reasons included not being eligible for coverage (27.0%), not needing or wanting coverage (26.6%), and signing up being too difficult (23.9%).

Reasons for Being Uninsured Among Uninsured Adults Ages 18-64, 2023

Not all workers have access to coverage through their jobs. In 2023, 64.7% of uninsured workers worked for an employer that did not offer them health benefits. Among uninsured workers who are offered coverage by their employers, cost is often a barrier to taking up the offer. Low-income families with employer-based coverage spend a significantly higher share of their income toward premiums and out-of-pocket medical expenses compared to those with income above 200% FPL.

A decade after the implementation of the ACA coverage options, 10 states have not adopted the Medicaid expansion, leaving 1.4 million uninsured people without an affordable coverage option. A coverage gap exists in states that have not adopted the expansion for poor adults who earn too much to qualify for Medicaid coverage but not enough to be eligible for subsidies in the Marketplace.

Lawfully-present immigrants generally must meet a five-year waiting period after receiving qualified immigration status before they can qualify for Medicaid. States have the option to cover eligible children and pregnant people without a waiting period, and as of January 2025, 38 states have elected the option for children, and 32 states have taken up the option for lawfully-present pregnant individuals. Under current law, lawfully-present immigrants are eligible for Marketplace tax credits, including those who are not eligible for Medicaid because they have not met the five-year waiting period. Undocumented immigrants are ineligible for federally-funded coverage, including Medicaid and Marketplace coverage, although some states provide fully state-funded health coverage to these individuals.

Health care provisions in the 2025 reconciliation package narrow eligibility for federally-subsidized health coverage, including Medicaid and CHIP, Medicare, and Marketplace subsidies, to a limited group of lawfully-present immigrants. These changes take effect on January 1, 2027 and are expected to increase the number of lawfully residing immigrants without health coverage.

Though financial assistance is available to many of the remaining uninsured under the ACA, not everyone who is uninsured is eligible for free or subsidized coverage. Nearly 6 in 10 (14.5 million) uninsured individuals in 2023 were eligible for financial assistance through Medicaid or subsidized Marketplace coverage (Figure 8). However, over 4 in 10 uninsured (10.9 million) were outside the reach of the ACA because their state did not expand Medicaid, their immigration status made them ineligible, or they were deemed to have access to an affordable Marketplace plan or offer of employer coverage (Figure 8).

Eligibility for Coverage Among Uninsured Population Ages 0-64, 2023

What are the Consequences of Being Uninsured?

Copy link to What are the Consequences of Being Uninsured?

Lacking health insurance in the United States can impact a person’s access to health care, their financial situation, and their health status. It can also broadly impact a community’s public health (illustrated by the COVID-19 pandemic) and the economy through lower productivity.

Adults who are uninsured are almost five times more likely than adults with insurance to report not having a usual source of care, which is often a key entry point for accessing health care whether for preventive services or for treating existing conditions. Consequently, in 2023, nearly half (46.6%) of uninsured adults ages 18-64 reported not seeing a doctor or health care professional in the past 12 months compared to 15.6% with private insurance and 14.2% with public coverage (Figure 9). Uninsured individuals are also more likely to face cost barriers to accessing needed care. In 2023, uninsured adults were nearly three times more likely to report not getting medical care due to cost compared to publicly insured adults and four times more likely than privately insured adults (22.6% vs 7.7% and 5.1%, respectively).

Barriers to Health Care Among Adults Ages 18-64 by Insurance Status, 2023 

The lack of access to health care and a delay in seeking care due to costs mean uninsured people are more likely to be hospitalized for avoidable health problems and to experience declines in their overall health. Research also shows that when they are hospitalized, uninsured people receive fewer diagnostic and therapeutic services and have higher mortality rates than those with insurance.

Uninsured individuals often face unaffordable medical bills when they do seek care, which can lead to medical debt and other forms of financial instability. Nearly half of uninsured adults reported difficulty paying for health care, compared to 21% of insured adults and over 8 in 10 (84%) uninsured adults said they worried that health care costs would put them in debt or increase their existing debt, compared to 71% of adults with insurance (Figure 10). Uninsured adults are also more likely to face negative consequences due to health care debt, such as using up savings, having difficulty paying other living expenses, or borrowing money.

Problems Paying for Health Care  and Worries About Health Care Debt by Insurance Status

Future Outlook

Copy link to Future Outlook

Driven by pandemic-era policies to promote health coverage, the number of people without insurance and the uninsured rate dropped to historic lows in recent years. Although millions of people lost Medicaid coverage during the unwinding of continuous enrollment, Medicaid enrollment remains higher than in February 2020, before the start of the pandemic. Enhanced Marketplace subsidies adopted during the pandemic led to record Marketplace signups, with enrollment topping 25 million in 2025. States have also taken action to reduce the number of people who are uninsured. In 2023, two states, North Carolina and South Dakota, newly adopted the Medicaid expansion, and several states have expanded state-funded coverage for certain individuals regardless of immigration status.

However, actions by Congress and the Trump Administration threaten to reverse these recent coverage gains. Congress passed the 2025 Federal Budget Reconciliation package on July 3, 2025, which makes significant changes to Medicaid and ACA Marketplaces, and President Trump signed the reconciliation package into law on July 4, 2025.  The Congressional Budget Office (CBO) estimates that the law will increase the number of people without health insurance by 10 million. The expiration of the enhanced premium tax credits for Marketplace enrollees, which will happen at the end of 2025 unless Congress takes action to extend them, will further increase the number of people without health insurance. CBO projects that over 14 million more people will be uninsured in 2034 due to the combined effects of the reconciliation package and the expiration of the enhanced Marketplace subsidies. In addition to these potential coverage losses, the Trump administration’s increased immigration enforcement activities are likely to have a broad chilling effect that could cause immigrants to decide to disenroll or not enroll themselves or their children, most of whom are U.S. citizens, in health coverage programs even if they are eligible due to immigration-related fears.

Enactment of the ACA helped close some gaps in our fragmented health coverage system and led to a significant decline in the number of people who were uninsured. Recent efforts built on that success to further shrink the share of people without insurance. Yet, despite this success and the ACA’s continued favorability—the public has a favorable view of the ACA by a 2 to 1 margin—policymakers enacted cuts to federal support for Medicaid and ACA coverage to fund other budget priorities. The impact on health coverage and people’s ability to access needed health care services will be significant.

Resources

Copy link to Resources

Citation

Copy link to Citation

Tolbert, Jennifer, Bell, Clea, Cervantes, Sammy & Singh, Rakesh, The Uninsured Population and Health Coverage. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-the-uninsured-population-and-health-coverage/ (date accessed).

International Comparison of Health Systems

KFF Authors:

Table of Contents

Introduction

Copy link to Introduction

Health systems aim to provide accessible, high-quality care that improves health outcomes at an affordable cost. One way to assess the performance of the United States’ health system is to benchmark it against those in similar countries.

Comparing health system performance internationally is complicated, though, as each country has unique political, economic, and social conditions. Because health spending and health outcomes are often correlated with a country’s wealth, this chapter focuses on comparisons between the U.S. and other large and wealthy OECD nations: Australia, Austria, Belgium, Canada, France, Germany, Japan, the Netherlands, Sweden, Switzerland, and the United Kingdom.

Despite spending far more money than any peer nation, Americans live shorter lives and often face more barriers to care. Some of this disparity can be attributed to aspects of the U.S. health system, but socioeconomic, health and other factors also play a role.

Health Insurance Systems and Coverage

Copy link to Health Insurance Systems and Coverage

From the late nineteenth to mid-twentieth centuries, many nations created health insurance systems that aimed to make health care accessible and affordable to their population. Some countries, like the United Kingdom, have health systems that are largely publicly funded and operated, while other countries, like Switzerland, have a compulsory private insurance system. Many countries’ health systems include a mix of private and public insurance. Regardless of financing mechanism, the health systems in many countries that are similarly large and wealthy as the U.S. are largely compulsory, resulting in universal or near-universal health coverage.

During this same period, the United States took a different approach, relying on a largely voluntary private insurance system that resulted in a substantial share of the population being uninsured. Despite decades of calls for a national public health insurance program, it was not until 1965 that two major public insurance programs were created – Medicare for people age 65 or older and Medicaid for low-income people – and it was not until the Affordable Care Act passed in 2010 that the U.S. health system was expanded to create near-universal eligibility for health insurance coverage for lawfully present residents. Even so, the U.S. health system is still largely voluntary and millions of people in the U.S. continue to go without insurance, often citing cost as a barrier.

Health Spending

Copy link to Health Spending

Wealthy countries, including the U.S., tend to spend more per person on health care and related expenses than lower-income countries. However, even among higher-income countries, the U.S. spends far more per person on health.

Spending Growth

Over the past five decades, the health spending gap between the U.S. and peer nations has widened. In 1970, the U.S. spent about 7% of its GDP on health, which was similar to spending in several comparable countries (the average of comparably wealthy countries was about 5% of GDP in 1970). The U.S. was relatively on pace with other countries until the 1980s, when health spending in the U.S. grew at a significantly faster rate relative to its GDP. 

The United States spends more per capita on total health expenditures, including government spending and household payments. In 2020, the U.S. spent 19.5% of its GDP on health consumption (up from 17.5% in 2019), largely due to the increased spending during the COVID-19 pandemic, along with the economic downturn. By 2023, health spending as a share of GDP had declined to 17.6% in the U.S.—but remains substantially higher than in peer countries.

Drivers of Health Spending

The largest category of health spending in both the U.S. and comparable countries is spending on inpatient and outpatient care, which includes payments to hospitals, clinics, and physicians for services and fees such as primary care or specialist visits, surgical care, provider-administered medications, and facility fees. Americans spent $8,353 per person on inpatient and outpatient care, compared to $3,636 in peer countries, on average. The U.S.’s higher spending on providers is driven more by higher prices than higher utilization of care. Patients in the U.S. have shorter average hospital stays and fewer physician visits per capita, while many hospital procedures have been shown to have higher prices in the U.S. Higher spending on inpatient and outpatient care drives most of the difference in health spending between the U.S. and its peers. In fact, the U.S. spends more on inpatient and outpatient care than most peer nations spend on their entire health systems (including long-term care, prescription drugs, administration, prevention, and other services).

The cost of prescription drugs is another factor that partially explains the U.S.’s higher health spending. Many of the same medications cost more in the U.S. than they do in other comparable nations. In 2022, the U.S. spent $1,765 per capita on prescription drugs and other medical goods (including over-the-counter and clinically delivered pharmaceuticals as well as durable and non-durable medical equipment). However, because prescription drugs represent a relatively small share of total health spending, even if per capita prescription drug spending in the U.S. were closer to that of comparable countries, that would make only a small dent in closing the gap on health spending.

Spending on health administration is similarly much higher in the U.S. than in comparable countries: $1,078.44 per capita. Administrative costs include spending on running governmental health programs and overhead from insurers, but exclude administrative expenditures from health care providers. This includes administrative spending for private health insurance, governmental health programs (such as Medicaid and Medicare), as well as other third-party payers and programs.

The U.S. also spends more per capita on preventive care than peer nations. Activities captured in this spending category vary among countries, but in the U.S., it generally consists of public health activities, including preventive health programs and education for immunizations, disease detection, emergency preparedness, and more. In the U.S., preventive care spending more than doubled between 2019 and 2020, from $343 to $741 per capita, but subsequently declined to $649 by 2022.

Meanwhile, the only category of spending in which the U.S. spends less than most comparable countries on a per-person basis is long-term care. Long-term care spending includes health and social services provided in long-term care institutions such as nursing homes as well as home- and community-based settings. After an increase from 2019 to 2020 at the onset of the COVID-19 pandemic, U.S. spending on long-term care declined by 4.9% between 2020 and 2021 but increased again by 5.4% between 2021 and 2022. Long-term care spending was already lower in the U.S. than in peer countries before the pandemic.

Health Outcomes

Copy link to Health Outcomes

Life Expectancy

Life expectancy is one of the most common measures of health outcomes. In 1980, the average American could expect to live 73.7 years – a similar life expectancy to residents of most wealthy countries. However, in subsequent years, life expectancy continued growing in most other nations at a pace far beyond that of the U.S.

In 1996, Japan became the first nation to report an average life expectancy of 80 years among its population. By 2012, all peer countries had also achieved this milestone. That same year, life expectancy in the U.S. was 78.5 years and began a decade-long plateau. By 2019, the life of the average U.S. resident would be almost four years shorter than the life of the average resident of these comparable nations (78.8 vs. 82.7 years).

This plateau and four-year gap were already highly concerning, but the health crisis brought on by the COVID-19 pandemic made the situation in the U.S. much worse. For the first time ever recorded, life expectancy dropped by almost two years, from 78.8 in 2019 to 77.0 in 2020. The pandemic was not unique to the United States, but this stunning life expectancy drop was – the average comparable nation saw a decline of less than half a year (82.7 to 82.3). By 2023, life expectancy rebounded to 78.4 years, still a full 1.3 years below pre-pandemic levels and over four years below the average among peer nations.

The life expectancy data presented here are period life expectancy estimates based on excess mortality observed in each year. Period life expectancy at birth represents the mortality experience of a hypothetical cohort if current conditions persisted into the future, and not the mortality experience of a birth cohort.

Years of Life Lost

The causes of this decrease in life expectancy are multifaceted. When people die before a certain age, the difference between their age at death and the specified age is recorded as life years lost. For example, when looking at years of life lost before age 75, a person who dies at age 60 would be considered to have lost 15 years of life. Examining the causes of these years of life lost can point to the factors which are decreasing life expectancy.

The United States had the highest rate of years of life lost per 100,000 population aged 75 years old in 2021, by a large margin. However, by examining the cause of these years of life lost, it is possible to notice where the U.S. underperforms. For example, the U.S. has a significantly higher rate of years of life lost due to heart disease, transport accidents, and accidental poisoning (a category that includes drug overdose).

While cancer is a common cause of premature years of life lost in the United States, most other countries have a similar rate of years of life lost due to cancer. This indicates that cancer is not a main cause of the discrepancy between the U.S. and peer nations.

Overall, the United States’ higher rates of premature death and disease burden do not necessarily reflect entirely on the quality of care that patients receive in doctors’ offices or hospitals. Life expectancy, mortality rates, and disease burden can also be influenced by factors outside of the health system, like socioeconomic conditions (e.g., income inequality, structural racism) and differences in health-related behaviors (e.g., diet, exercise, drug use). Children and teens in the U.S. are less likely to make it to adulthood than in peer countries, with the U.S having higher rates of motor vehicle accidents, firearm deaths, and suicide deaths among children and teens.

Quality of Care

Copy link to Quality of Care

Another, more direct way to measure the performance of the health system is to examine the quality of care provided in a hospital or clinical setting. However, inconsistent and imperfect quality metrics make it difficult to compare quality of care in the U.S. and its peers.

In comparison to peer nations, across the limited measures available internationally, the U.S. performs better on some and worse on other indicators of quality of care. For example, the U.S. performs worse on certain measures of treatment outcomes (such as maternal mortality) and some patient safety measures (such as obstetric trauma with instrument and medication or treatment errors). The U.S. performs similarly to or better than peer nations in other measures of treatment outcomes (such as mortality rates within 30 days of acute hospital treatment) and patient safety (such as rates of post–operative sepsis).

Hospital Mortality Rates

Mortality within 30 days of being admitted to a hospital is not entirely preventable, but high quality of care can reduce the mortality rate for certain diagnoses. The 30-day mortality rates after hospital admissions for heart attacks (acute myocardial infarction) are similar in the U.S. and the average of comparable countries. However, the 30-day mortality rates for ischemic strokes (caused by blood clots) were 4.5 deaths per 100 patients in the U.S. in 2022, compared to an average of 6.9 deaths per 100 patients in similar countries. Rates of mortality after hemorrhagic stroke (caused by bleeding) are also lower in the U.S. While the U.S. has lower rates of mortality due to these conditions than the average across peer nations, it is important to note that several peer nations have lower rates than the U.S.

Maternal Health

While wealth and economic prosperity are highly correlated with lower maternal mortality rates, the U.S. is an outlier with the highest rate of pregnancy-related deaths (18.6 deaths per 100,000 live births in 2023) when compared to similar countries (5.1 deaths per 100,000 live births). 

Within the U.S., there are significant racial disparities in maternal mortality rates. The maternal mortality rate for Black mothers is about 3 times the rate for White mothers — a disparity that persists across age and socioeconomic groups. Every race and ethnicity, socioeconomic, and age group in the United States sees higher maternal mortality rates than the average in comparable countries. Maternal mortality in the U.S. has risen in recent years, sparking concern from the medical community and policymakers. 

Obstetric trauma is more likely to occur in deliveries where instruments are utilized (i.e., forceps). The rate of obstetric trauma during deliveries with an instrument in the U.S. was 11.7 per 100 vaginal deliveries in 2022, higher than most comparable countries with available data. The rate of obstetric trauma during deliveries without an instrument in the U.S. was 1.7 per 100 vaginal deliveries in 2022, on the lower end among comparable countries with available data.

Hospital Admissions

Hospital admissions for certain chronic diseases, such as cardiac conditions, chronic obstructive pulmonary diseases (COPD), asthma, and diabetes, can arise for a variety of reasons, but preventive services — or lack thereof — play a large role. Hospital admission rates in the U.S. are higher than in comparable countries for congestive heart failure and complications due to diabetes, and some admissions for these chronic conditions could be avoided through primary care.

Post-Operative Complications

Rates of post-operative complications are an important measure of hospital safety. Pulmonary embolisms and deep vein thromboses are common complications after major surgeries, such as hip or knee replacement. The prevalence of post-operative clots for these procedures is higher in the U.S. than in the U.K., Sweden, Belgium, and the Netherlands, but lower than in Australia.

Sepsis is a life-threatening complication of infection that can lead to organ failure, shock, or death. Rates of post-operative infections and sepsis are an important marker of care quality for patients undergoing surgery, because this is a major source of morbidity and mortality that can sometimes be prevented. Prevention is multifactorial and can involve proper operative techniques and training, hygiene and safety protocols, and antibiotic utilization, among other things. The rate of post-operative sepsis following abdominal surgery is just under 2% in the U.S., lower than in most peer countries that report data.

Access to Care

Copy link to Access to Care

Out-of-Pocket Costs

Universal coverage means all residents have health insurance, but it does not mean health care is free. In many countries people contribute to health care costs through both out-of-pocket expenses—such as copays, coinsurance, and deductibles—as well as insurance premiums. Even in countries with universal coverage, residents often have at least nominal out-of-pocket costs. In fact, people in Switzerland pay more out-of-pocket on health care ($1,988), on average, than Americans do ($1,425) per capita.

Costs are a common barrier to accessing health care in the U.S. More than 1 in 4 Americans report skipping consultations, tests, treatment, or follow-up, and 21% report skipping medication. Only 9.2% of the United States population is uninsured, so these numbers include individuals who have health insurance, but still find medical care unaffordable. While cost-related access barriers are particularly prevalent in the U.S., residents of other countries with universal coverage also report skipping care due to costs.

Appointment Availability

Cost is not the only reason why a person may miss or delay needed medical care. The availability of physicians can also impact access to care. Among people who needed same or next-day medical care, about half (51%) of Americans were able to make a timely appointment, which is somewhat below the average of peer nations (57%).

Physicians

The U.S. has just 2.7 practicing physicians per 1,000 residents, compared to an average of 3.8 among peer nations. Also of concern in the U.S. is the ratio of primary to specialty care providers. Most other nations have somewhere between one-quarter and one-half physicians employed in primary care. Primary care is an integral part of the health system in many nations – a patient sees a primary care physician for most illnesses or injuries and only goes to a specialist or hospital if their primary care doctor decides it is necessary. In the United States, however, only 12% of doctors are general physicians, including primary care physicians.

The U.S. faces this physician shortage and high rates of specialization in part due to how medical education is structured. The U.S. has kept a tight lid on the number of medical schools, as well as the number of training spots available to new doctors. Furthermore, the higher education system in the U.S. places the burden of financing an education on the student, and university tuition is more expensive than in many peer countries. As a result, students borrow money, and most graduate from medical school with a significant amount of debt. Because primary care generally comes with a lower salary, some new physicians may pursue a higher-paid specialty, even if they would rather work in primary care.

Additionally, the U.S. has only 0.15 psychiatrists per 1,000 residents, the lowest of all peer nations. Although the U.S. has a high number of specialist providers, only 6% are psychiatrists, compared to an average of 10% of specialists in other countries examined. Despite clear and increasing demand for mental health treatment, psychiatry remains one of the lowest-paid physician specialties in the United States.

Future Outlook

Copy link to Future Outlook

The outlook of health systems will be shaped by various factors, including political and policy changes, technological advancements, economic and demographic shifts, social factors, and unforeseen events–as the COVID-19 pandemic demonstrated. Here are some issues to watch:

Health Outcomes: The United States was already performing worse than its peers across a wide range of health outcomes, but the COVID pandemic widened the gap, and it is not yet clear whether life expectancy and other measures will recover as quickly in the U.S. as in peer nations. In addition to the pandemic recovery, both the U.S. and peer countries face the challenge of aging populations and increases in chronic conditions, leading to increased demand for health care services and long-term care.

Access to Care: Unlike the U.S., other large and wealthy nations have long achieved universal or near-universal health coverage and offer more robust access to care. While the U.S. recently reached a record-high insurance coverage rate, the tax and spending legislation signed by President Trump includes the biggest reduction ever in federal spending on Medicaid and the Affordable Care Act Marketplaces—changes that are projected to increase the number of people uninsured by millions in the coming years. Moreover, even those with insurance in the U.S. often face high out-of-pocket costs, leading many to forgo needed care or incur medical debt.

Quality of Care: The adoption of new technologies will shape care delivery in both the United States and in other countries. Electronic health records, telemedicine, artificial intelligence, and other digital health tools are becoming more prevalent globally. However, many digital health tools are new, untested, and have unknown implications for quality of care.

Health Spending: Most peer nations place a strong emphasis on cost containment and efficiency and achieve this through regulation of and negotiation with health providers. In the U.S., by contrast, the federal and state governments less directly control commercial health insurance prices. However, with the passage of the Inflation Reduction Act, Medicare has negotiated drug prices for a selection of high cost drugs. There will likely be ongoing debate about further actions the federal government can take to lower drug prices, as well as taking other steps to restrain prices of health care generally.

Resources

Copy link to Resources

Health Costs:

Health Outcomes:

Access and Quality of Care

Citation

Copy link to Citation

Wager, E. & Cox, C., International Comparison of Health Systems. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-international-comparison-of-health-systems/ (date accessed). 

Medicaid 101

Table of Contents

Introduction

Copy link to Introduction

Medicaid is the primary program providing comprehensive coverage of health and long-term care to about 80 million low-income people in the United States. Medicaid accounts for nearly one-fifth of health care spending (and over half of spending for long-term care) and a large share of state budgets. Medicaid is jointly financed by states and the federal government but administered by states within broad federal rules. Because states have the flexibility to determine what populations and services to cover, how to deliver care, and how much to reimburse providers, there is significant variation across states in program spending and the share of people covered by the program.  Changes to Medicaid and the Affordable Care Act included in the tax and spending budget reconciliation law enacted in July 2025 are expected to reduce federal Medicaid spending by $911 billion over 10 years and reduce the number of people with health insurance by 10 million (three-quarters of which stems from the cuts to Medicaid).

What Is Medicaid?

Copy link to What Is Medicaid?

Medicaid is the primary program providing comprehensive coverage of health care and long-term care to about 80 million low-income people in the United States. Medicaid accounts for nearly one-fifth of health care spending (and half of spending for long-term care) and a large share of state budgets (Figure 1).

Medicaid Finances Nearly One Fifth of Health Care Spending

Subject to federal standards, states administer Medicaid programs and have flexibility to determine what populations and services to cover, how to deliver care, and how much to reimburse providers. States can obtain Section 1115 waivers to test and implement approaches that differ from what is required by federal statute if the Secretary of Health and Human Services (HHS) determines the waivers would advance program objectives. Because of this flexibility, there is significant variation across state Medicaid programs, and, as a result, the share of state residents covered by the program (Figure 2).

Nationally, One in Five People Have Medicaid, but This Varies Across the States (Choropleth map)

How Has Medicaid Evolved Over Time?

Copy link to How Has Medicaid Evolved Over Time?

Title XIX of the Social Security Act and a large body of federal regulations and sub-regulatory guidance govern the program, defining federal Medicaid requirements and states’ options and authorities. At the federal level, the Centers for Medicare and Medicaid Services (CMS) within the Department of Health and Human Services (HHS) administers Medicaid and oversees states’ programs. States may choose to participate in Medicaid, but if they do, they must comply with core federal requirements. Not all states opted to participate in Medicaid immediately after its enactment in 1965, but by the 1980s, all states had opted in. Medicaid coverage was historically tied to cash assistance—either Aid to Families with Dependent Children (AFDC) or federal Supplemental Security Income (SSI). Over time, Congress expanded federal minimum requirements and provided new coverage requirements and options for states, especially for children, pregnant women, and people with disabilities. In 1996, legislation replaced Aid to Families with Dependent Children with Temporary Assistance to Needy Families (TANF) and severed the link between Medicaid eligibility and cash assistance for children, pregnant women, and low-income parents. The Children’s Health Insurance Program (CHIP) was established in 1997 to cover low-income children above the cut-off for Medicaid with an enhanced federal match rate (Figure 3).

In 2010, the Affordable Care Act (ACA) expanded Medicaid to nearly all nonelderly adults with income up to 138% FPL ($21,597 annually for an individual in 2025) through a new coverage pathway for parents with incomes above states’ mandatory eligibility levels for parents/caretakers and adults without dependent children who had traditionally been excluded from Medicaid coverage. However, the ACA Medicaid expansion coverage is effectively optional for states because of a 2012 Supreme Court ruling. As of July 2025, 41 states, including Washington, D.C., have expanded Medicaid (Figure 4). States receive a higher rate of federal matching funding for people who are enrolled through the expansion coverage pathway. Under the ACA, all states were also required to modernize and streamline Medicaid eligibility and enrollment processes to help individuals obtain and maintain coverage.

41 States Including DC Have Expanded Medicaid (Choropleth map)

The COVID-19 pandemic profoundly affected Medicaid spending and enrollment. At the start of the pandemic, Congress enacted legislation that included a requirement that Medicaid programs keep people continuously enrolled in exchange for enhanced federal funding. As a result, Medicaid/CHIP enrollment grew substantially, and the uninsured rate dropped. The unwinding of these provisions started on April 1, 2023, and millions were disenrolled from Medicaid; however, Medicaid enrollment remains higher than prior to the start of the pandemic in February 2020.

Passage of the tax and spending reconciliation budget bill in July 2025 included significant changes to Medicaid that are expected to reduce federal Medicaid funding and reduce Medicaid enrollment over the next 10 years relative to what would have been expected under current law. For the first time, the law conditions Medicaid eligibility for Medicaid expansion enrollees on meeting work and reporting requirements.  These work requirements, which will go into effect on January 1, 2027, or sooner at state option, represent the largest source of federal Medicaid funding reductions and the largest source of enrollment declines in the law. The law makes other changes. Beyond work requirements, the largest cuts to Medicaid stem from provisions that would: reduce and limit provider taxes, a mechanism that nearly all states use to finance the state share of Medicaid; reduce the payments states require managed care organizations to make to health care providers (“state-directed payments”); delaying enforcement of certain provisions in the Biden administration’s rules simplifying Medicaid eligibility and renewal processes; and increasing frequencies of eligibility redeterminations for expansion enrollees. Combined, those changes and work requirements account for nearly 90% of the expected cuts in federal spending according to the Congressional Budget Office (CBO).

How Is Medicaid Financed?

Copy link to How Is Medicaid Financed?

States are guaranteed federal matching dollars without a cap for qualified services provided to eligible enrollees. The match rate for most Medicaid enrollees is determined by a formula in the law that provides a match of at least 50% and provides a higher federal match rate for states with lower per capita income (Figure 5). States may receive a higher match rate for certain services and populations. The ACA expansion group is financed with a 90% federal match rate, so states pay 10%, and the American Rescue Plan Act included an additional temporary fiscal incentive to states that newly adopt the Medicaid expansion; however, the tax and spending law eliminated the incentive, effective January 1, 2026. In FY 2023, Medicaid spending totaled $880 billion of which 69% was federal spending. Medicaid spending growth typically accelerates during economic downturns as enrollment increases. Spending growth also peaked after the implementation of the ACA and, more recently, due to enrollment growth tied to the pandemic-related continuous enrollment provision.

Overall, Medicaid accounts for a large share of most states’ budgets and is often central to state fiscal decisions; however, state spending on Medicaid is second to state spending on elementary and secondary education, and the program is also the largest source of federal revenue for states. In state fiscal year 2023, Medicaid accounted for 30% of total state expenditures, 15% of expenditures from state funds (general funds and other funds), and 57% of expenditures from federal funds received by the state.

Social Security, Medicare , and Medicaid are the three main entitlement programs, accounting for 41% of all federal outlays in FFY 2024. Of these three programs, Medicaid is the smallest in terms of federal outlays, though it covers more people than Medicare or Social Security. Overall, federal spending on domestic and global health programs and services accounted for 29% of net federal outlays in FFY 2023, including spending on Medicare (13%), Medicaid and CHIP (10%), and other health spending (6%). Dating back to the 1980s, there have been efforts to limit federal financing for Medicaid either through a block grant to states or through a cap on spending per enrollee as a way to help reduce federal spending. Such efforts could shift costs to states, forcing them to make tough choices about whether to pay for the federal cuts, which would require higher taxes or reductions in non-Medicaid state spending, or to reduce Medicaid spending by limiting Medicaid eligibility, covering fewer benefits, or paying less to providers. Although early discussions over the tax and spending law included proposals that would have reduced the federal Medicaid match rate and imposed a cap on per-enrollee spending, these changes to Medicaid financing were not included in the final version of the bill that passed.

Medicaid is Jointly Financed by the Federal Government and States

Who Is Covered by Medicaid?

Copy link to Who Is Covered by Medicaid?

Medicaid is an entitlement, meaning individuals who meet eligibility requirements are guaranteed coverage. The federal government sets minimum eligibility standards, but states may expand coverage beyond these minimum requirements.  Federal minimum eligibility levels for children and pregnant individuals are set at 133% of the federal poverty level (FPL) with a mandatory 5 percentage point income disregard or effectively 138% FPL ($36,777 for a family of 3 in 2025); however, median eligibility levels for these groups were 255% FPL for children and 213% FPL for pregnant individuals as of January 2025. As a result of the ACA, the median coverage level for parents and adults without dependent children is 138% FPL, but for states that have not adopted the ACA expansion, the median eligibility for parents was 33% FPL. In non-expansion states, adults without dependent coverage are not eligible for Medicaid coverage and those with incomes below the FPL fall into the coverage gap.

Medicaid coverage is also available to certain individuals who qualify on the basis of being age 65 and older or having a disability. These coverage categories are referred to as “non-MAGI” pathways because they do not use the Modified Adjusted Gross Income (MAGI) financial methodology that applies to pathways for pregnant people, parents, and children with low incomes. In addition to considering advanced age, disability status, and income, many non-MAGI pathways also have asset limits. Medicaid generally covers individuals who qualify for Supplemental Security Income (SSI), but nearly all other non-MAGI pathways are optional, resulting in substantial state variation.  Each group has different rules about income and assets, making eligibility complex (Figure 6).

Medicaid Income Eligibility Limits Vary by Population, Pathway, and State

Medicaid coverage is limited for immigrants, and except for emergency services, Medicaid coverage is not available for undocumented immigrants. A number of states, however, use state funds to provide coverage to all or some undocumented immigrants.

While Medicaid covers 1 in 5 people living in the United States, Medicaid is a particularly significant source of coverage for certain populations. In 2023, Medicaid covered 4 in 10 children, 8 in 10 children in poverty,  1 in 6 nonelderly adults, and 6 in 10 nonelderly people in poverty. Relative to White children and adults, Medicaid covers a higher share of Black, Hispanic, and American Indian or Alaska Native (AIAN) children and adults. Medicaid covers over 1 in 3 people with disabilities overall (4 in 10 people with disabilities ages 19-64), who are defined as having one or more difficulty related to hearing, vision, cognition, ambulation, self-care, or independent living (Figure 7).

Medicaid provides coverage for a number of special populations.  For example, Medicaid covers 41% of all births in the United States, 42% of children with special health care needs, 5 in 8 nursing home residents, 29% of non-elderly adults with any mental illness, and 40% of non-elderly adults with HIV. Medicaid pays Medicare premiums and often provides wraparound coverage for services not covered by Medicare (like most long-term care) for nearly 1 in 5 Medicare beneficiaries (13 million).  Medicaid is a key source of coverage for individuals experiencing homelessness and those transitioning out of carceral settings, particularly in states that have adopted the Medicaid expansion.

Among the non-elderly covered by Medicaid, nearly half are children under age 19, 6 in 10 are people of color, 57% are female, and three-quarters are in a family with a full- or part-time worker. Even though most adult Medicaid enrollees are working, many do not have an offer of employer-sponsored coverage, or it is not affordable.

Medicaid is a Key Source of Coverage for Certain Populations

What Benefits Are Covered by Medicaid?

Copy link to What Benefits Are Covered by Medicaid?

Medicaid covers a broad range of services to address the diverse needs of the populations it serves. In addition to covering the services required by federal Medicaid law, all states elect to cover at least some services that are not mandatory (Figure 8). All states cover prescription drugs, and most states cover physical therapy, eyeglasses, and dental care. Medicaid provides comprehensive benefits for children, known as Early Periodic Screening Diagnosis and Treatment (EPSDT) services. EPSDT is especially important for children with disabilities because it allows children access to a broader set of benefits to address complex health needs than what is traditionally covered by private insurance. Unlike commercial health insurance and Medicare, Medicaid also covers non-emergency medical transportation, which helps enrollees get to appointments, and long-term care, including nursing home care and many home care services (also known as home and community-based services, or HCBS). Coverage for long-term care is mandatory for nursing facilities, but most coverage of home care is optional. In recent years, states have expanded coverage of behavioral health services and benefits to help enrollees address social determinants of health (SDOH) like nutrition or housing.

Most of Medicaid's Mandatory Benefits are for Acute Care

What Long-term Care (LTC) is Covered by Medicaid?

Copy link to What Long-term Care (LTC) is Covered by Medicaid?

Most people age 65 and older and many people under age 65 with disabilities have Medicare, but Medicare does not cover most LTC; instead, Medicaid is the primary payer for LTC. LTC encompasses the broad range of paid and unpaid medical and personal care services that assist with activities of daily living (such as eating, bathing, and dressing) and instrumental activities of daily living (such as preparing meals, managing medication, and housekeeping). They are provided to people who need such services because of aging, chronic illness, or disability. These services include nursing facility care, adult daycare programs, home health aide services, personal care services, transportation, and supported employment. They may be provided over several weeks, months, or years, depending on an individual’s health care coverage and level of need. There have been longstanding challenges finding enough workers to provide LTC for all people who need such services, and the COVID-19 pandemic exacerbated those issues considerably. As the population ages and advances in medicine and technology enable people with serious disabilities to live longer, the number of people in need of LTC is expected to grow.

In 2024, the median annual costs of care in the U.S. were $127,750 for a private room in a nursing home, $70,800 for an assisted living facility, and $77,792 for a home health aide. Medicare provides home health and skilled nursing facility care under specific circumstances, but the Medicare benefit is considered “post-acute” care and generally not available for people needing services on an ongoing basis. Medicaid plays a key role in access to LTC for people who qualify because LTC costs are difficult for most people to afford when paying out-of-pocket. In some cases, people only qualify for Medicaid after exhausting their savings on the costs of LTC. In 2023, Medicaid paid 61% of the $459 billion spent on LTC in the U.S. (Figure 9).

Medicaid Paid for Over Half of the $459 Billion That the US Spent on LTC in 2023, Most of Which Went to Home Care

LTC may be provided in various settings broadly categorized as institutional or non-institutional. Institutional settings include nursing facilities and intermediate care facilities for people with intellectual disabilities. Services provided in non-institutional settings are known as home care (also known as home and community-based services, or HCBS), and these settings may include a person’s home, adult day care centers, assisted living settings, and group homes. Federal Medicaid statutes require states to cover institutional LTC and home health, but nearly all home care is optional. Even without a mandate to cover home care, Medicaid LTC spending has shifted from institutional to non-institutional settings over time. In 2023, most spending for LTC in the U.S. was for home care (Figure 9). That shift reflects beneficiary preferences for receiving care in non-institutional settings and requirements for states to provide services in the least restrictive setting possible stemming from the Olmstead decision. In 2023, there were 6.3 million people who used Medicaid LTC, of which 4.9 million (77%) used home care and 1.4 million (23%) used institutional care (Figure 10). While overall, over three-quarters of people who used Medicaid LTC exclusively used home care services, the share varied across states (Figure 10).  To qualify for coverage of LTC under Medicaid, people must meet state-specific eligibility requirements regarding their levels of income, wealth, and functional limitations.

The Percentage of People Who Used Medicaid LTC in Home and Community Settings Was 77% Nationally But Varied Across States (Stacked column chart)

How Much Does Medicaid Spend and on What?

Copy link to How Much Does Medicaid Spend and on What?

Managed care is the dominant delivery system for Medicaid enrollees with 75% of Medicaid beneficiaries enrolled in comprehensive managed care organizations (MCOs). Medicaid MCOs provide comprehensive acute care and, in some cases, LTC to Medicaid beneficiaries and are paid a set per member per month payment for these services. In FFY 2023, payments to managed care and health plans accounted for the largest share (55%) of Medicaid spending, with capitated payments to comprehensive MCOs accounting for 52% of Medicaid spending and payments to other Medicaid managed care (e.g., primary care case management (PCCM) arrangements or specialty plans) accounting for another 3% (Figure 11). Smaller shares of total Medicaid spending in FFY 2023 were for fee-for-service acute care (21%), fee-for-service LTC (19%), Medicaid spending for Medicare premiums on behalf of enrollees who also have Medicare (3%), and disproportionate share hospital (DSH) payments (2%).

Payments to Comprehensive MCOs Account for More Than Half of Total National Medicaid Spending

Medicaid spending is driven by multiple factors, including the number and mix of enrollees, their use of health care and long-term care, the prices of Medicaid services, and state policy choices about benefits, provider payment rates, and other program factors. During economic downturns, enrollment in Medicaid grows, increasing state Medicaid costs while state tax revenues are declining. Due to the federal match, as spending increases during economic downturns, so does federal funding. During the pandemic-induced recession and the two economic downturns prior to the pandemic, Congress enacted legislation that temporarily increased the federal share of Medicaid spending to provide increased support for states to help fund Medicaid. High enrollment growth rates, tied first to the Great Recession, then ACA implementation, and later the pandemic, were the primary drivers of total Medicaid spending growth over the last two decades (Figure 12).

Line graph of percent change in Medicaid enrollment and total spending shows Medicaid enrollment is expected to decline by xxx% as total spending growth slows to xxx%.

How Much Does Medicaid Spending Vary Across Enrollee Groups and States?

Copy link to How Much Does Medicaid Spending Vary Across Enrollee Groups and States?

People eligible based on being age 65 or older or based on a disability comprise about 1in 5 enrollees but account for more than half of Medicaid spending, reflecting high health care needs and in many cases, use of LTC (Figure 13).

People Eligible for Medicaid Based on Disability or Age (65+) Accounted for 1 in 5 Enrollees but Over Half of All Spending in 2023 (Stacked column chart)

Across the states, spending per full-benefit enrollee ranged from a low of $4,780 in Alabama to $12,295 in the District of Columbia in 2023. Variation in spending across the states reflects considerable flexibility for states to design and administer their own programs – including what benefits are covered and how much providers are paid — and variation in the health and population characteristics of state residents. Within each state, there is also substantial variation in the average costs for each eligibility group, and within each eligibility group, per-enrollee costs may vary significantly, particularly for individuals eligible based on disability (Figure 14).

Medicaid Spending Per Enrollee Ranged From Under $6,000 to Over $12,000

In 2023, people who used Medicaid LTC comprised 6% of Medicaid enrollment but 36% of federal and state Medicaid spending (Figure 15). High per-person Medicaid spending among enrollees who use LTC likely reflects the generally high cost of LTC and more extensive health needs among such groups that lead to higher use of other health care services and drugs as well.

Medicaid Enrollees Who Used LTC Had Disproportionately High Medicaid Spending in 2023 (Stacked column chart)

How Are Medicaid Services Delivered?

Copy link to How Are Medicaid Services Delivered?

As of July 2024, 42 states (including Washington, D.C.) contract with comprehensive, risk-based managed care plans – often administered by private insurance companies – to provide care to at least some of their Medicaid beneficiaries (Figure 16). Medicaid MCOs provide comprehensive acute care (i.e., most physician and hospital services) and, in some cases, LTC to Medicaid beneficiaries and are paid a set per member per month payment for these services. Medicaid MCOs represent a mix of private for-profit, private non-profit, and government plans. States have increased their reliance on MCOs with the aim of improving access to certain services, enhancing care coordination and management, and making future costs more predictable. While the shift to MCOs has increased budget predictability for states, the evidence about the impact of managed care on access to care, costs, and outcomes is both limited and mixed. Children and adults are more likely to be enrolled in MCOs than adults aged 65 and older and people eligible because of a disability; however, states are increasingly including beneficiaries with complex needs in MCOs. States are also increasingly leveraging Medicaid MCOs to help identify and address social determinants of health and to reduce health disparities.

As of July 2024, 42 States Used Capitated Managed Care Models to Deliver Services in Medicaid

What Is Known About Access in Medicaid?

Copy link to What Is Known About Access in Medicaid?

A large body of research shows that Medicaid enrollees have substantially better access to care than people who are uninsured (who are also primarily low-income) and are less likely to postpone or go without needed care due to cost. Key measures of access to care and satisfaction with care among Medicaid enrollees are generally comparable to rates for people with private insurance (Figure 17). Given Medicaid enrollees have low incomes, federal rules include protections to limit out-of-pocket costs that can help improve access.  A 2023 KFF Survey of Consumer Experiences with Health Insurance found Medicaid enrollees report fewer cost-related problems compared to those with Marketplace or employer coverage. While most Medicaid enrollees will continue to be protected against large out-of-pocket costs, the tax and spending law newly requires states to impose cost sharing of up to $35 on certain services on Medicaid expansion adults who have incomes 100% - 138% FPL.

Longstanding research shows that Medicaid eligibility during childhood is associated with positive effects on health (including reduced avoidable hospitalizations and mortality) and impacts beyond health, such as improved long-run educational attainment. Early and updated research findings show that state Medicaid expansions to low-income adults are associated with increased access to care, increased economic security, improved self-reported health status, and other outcomes including increased early-stage cancer diagnosis rates, lower mortality rates for certain conditions (e.g., cancer, cardiovascular disease, liver disease), decreased maternal mortality, improved treatment management for conditions (e.g., diabetes, HIV), and improved outcomes related to substance use disorders. Gaps in access to certain providers (e.g., psychiatrists and dentists) are an ongoing challenge in Medicaid that may reflect system-wide problems, but may be exacerbated by provider shortages in low-income communities, Medicaid’s lower physician payment rates, and lower Medicaid physician participation compared with private insurance. In 2021, MACPAC found physicians were less likely to accept new Medicaid patients (74%) than those with Medicare (88%) or private insurance (96%), but these rates may vary by state, provider type, and setting. Medicaid acceptance was much higher where physicians practiced in community health centers, mental health centers, non-federal government clinics, and family clinics compared to the average for all settings. Provider participation rates may contribute to findings that Medicaid enrollees may experience more difficulty obtaining health care than those with private insurance.  A 2023 KFF Survey of Consumers found Medicaid enrollees report more problems with prior authorization and provider availability compared to people with other insurance types.

People with Medicaid Report Similar Access to Care as People with Private Insurance and Much Better Access to Care than People who are Uninsured

How Do Medicaid Demonstration Waivers Work?

Copy link to How Do Medicaid Demonstration Waivers Work?

Section 1115 demonstration waivers offer states the ability to test new approaches in Medicaid that differ from what is required by federal statute, if CMS determines that such proposals are “likely to assist in promoting the objectives of the Medicaid program.” Nearly all states have at least one active Section 1115 waiver and some states have multiple 1115 waivers. Section 1115 waivers have been used over time and generally reflect priorities identified by the states as well as changing priorities from one presidential administration to another (Figure 18). Waivers have been used to expand coverage or benefits, change policies for existing Medicaid populations (e.g., testing premiums or other eligibility requirements), modify delivery systems, restructure financing or authorize new payments (e.g., supplemental payments or incentive-based payments), as well as make other program changes. 

Activity from the first Trump administration and the Biden administration tested how 1115 waivers can be used to advance administrative priorities and also tested the balance between states’ flexibility and discretion by the federal government. The first Trump administration’s Section 1115 waiver policy emphasized work requirements and other eligibility restrictions, payment for institutional behavioral health services, and capped financing. The Biden administration withdrew waiver approvals with work requirements, phased out approval of premium requirements, and instead encouraged states to propose waivers that expand coverage, reduce health disparities, advance “whole-person care,” and improve access to behavioral health care. Areas of focus during the Biden administration included leveraging Medicaid to address health-related social needs (including housing instability, homelessness, nutrition insecurity) and to provide health care to individuals transitioning from incarceration back into the community. Several states also received approval to provide multi-year continuous Medicaid coverage for children. Recent actions from the new Trump administration could signal efforts to curtail waivers related to social determinants of health, continuous eligibility and to limit 1115 waiver financing tools and flexibility. In addition, several states are seeking approval for work requirements waivers. Although the tax and spending reconciliation law now includes a national work requirement, some states may continue to pursue waivers to implement work requirements prior to January 1, 2027 when the national requirement goes into effect.

Section 1115 Waivers Reflect Changing Priorities From One Presidential Administration to Another (Table)

Various types of waivers and other emergency authorities can also be used to respond to emergencies. These authorities can help expand Medicaid capacity and focus on specific services, providers, or groups of enrollees that may be particularly impacted. During the COVID-19 pandemic, all 50 states and Washington, D.C. received approval to make changes using emergency authorities to facilitate access to care by expanding telehealth, eligibility, benefits and help address workforce issues for home- and community-based services.

Future Outlook

Copy link to Future Outlook

Looking to the future, Medicaid faces a number of challenges, including: 

  • How will the new work requirements, eligibility and cost sharing changes affect Medicaid enrollment and access to care, particularly for adults covered through the Medicaid expansion?
  • What impact will the Medicaid changes have on the number of people without health insurance?
  • How will states respond to federal Medicaid spending cuts and limits on their ability to use provider taxes to help finance the non-federal share of Medicaid spending?
  • How will the cuts in Medicaid spending and enrollment affect health care providers (including rural providers) and the broader health care system? To what extent will a new temporary rural health fund totaling $50 billion blunt some of the effects of the cuts?
  • Will administrative actions and federal funding cuts for Medicaid as well as broader federal changes in immigration policy affect Medicaid payment rates for long-term care and the long-term care workforce?
  • Will Congress move to reverse some of the Medicaid cuts before they go into effect?

Policy changes to Medicaid have implications for the roughly 80 million people who rely on the program for health coverage, state and federal budgets and spending, and health care providers, including nursing facilities and home care providers. As the source of nearly one fifth of total health care spending, these changes will also have implications for the broader health care system. Changes in Medicaid enrollment will also affect overall coverage trends. Declines in Medicaid enrollment can be expected to increase the number of people who are uninsured, jeopardizing improvements in the affordability of and access to care for potentially millions of people.  

Resources

Copy link to Resources

Citation

Copy link to Citation

Rudowitz, R., Tolbert, J., Burns, A., Hinton, E., Chidambaram, P., & Mudumala, A., Medicaid 101. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-medicaid/ (date accessed)

ACA Marketplace Premium Payments Would More than Double on Average Next Year if Enhanced Premium Tax Credits Expire

Authors: Justin Lo, Larry Levitt, Jared Ortaliza, and Cynthia Cox
Published: Sep 30, 2025

Affordable Care Act (ACA) enhanced premium tax credits are set to expire at the end of this year. Enhanced premium tax credits were introduced in 2021 and later extended through the end of 2025 by the Inflation Reduction Act. The enhanced tax credits both increased the amount of financial assistance already eligible ACA Marketplace enrollees received as well as made middle-income enrollees with income above 400% of federal poverty guidelines newly eligible for premium tax credits.

Since the introduction of the enhanced premium tax credits, enrollment in the Marketplace has more than doubled from about 11 to over 24 million people, the vast majority of whom receive an enhanced premium tax credit. If enhanced tax credits expire, many Marketplace enrollees will continue to qualify for a smaller tax credit, while others will lose eligibility altogether and be hit by a “double whammy” of losing their entire tax credit and being on the hook for rising premiums.

Since 2014, the ACA has capped how much subsidized enrollees pay for their health insurance premiums at a certain percent of their income, on a sliding scale, with the federal government covering the remainder in the form of a tax credit. Enhanced tax credits work by further lowering the share of income ACA Marketplace enrollees pay for a plan. For example, with the enhanced tax credits in place, an individual making $28,000 will pay no more than around 1% ($325) of their annual income towards a benchmark plan. If the enhanced tax credits expire, this same individual would pay nearly 6% of their income ($1,562 annually) towards a benchmark plan in 2026. In other words, if the enhanced tax credits expire, this individual would experience an increase of $1,238 in their annual premium payments net of the tax credit.
ACA Marketplace Enrollees Will Pay More for Benchmark Coverage if Enhanced Tax Credits Expire (Table)

A previous KFF analysis, based on data released by the federal government, showed the enhanced premium tax credits saved subsidized enrollees an average of $705 annually in 2024, bringing their annual premium payment down to $888. Without the enhanced premium tax credits, annual premium payments in 2024 would have averaged $1,593 (over 75% higher than the actual $888). More recent data have not been released.

Based on the earlier federal data and more recent other publicly available information, KFF now estimates that, if Congress extends enhanced premium tax credits, subsidized enrollees would save $1,016 in premium payments over the year in 2026 on average. In other words, expiration of the enhanced premium tax credits is estimated to more than double what subsidized enrollees currently pay annually for premiums—a 114% increase from an average of $888 in 2025 to $1,904 in 2026. (The average premium payment net of tax credits among subsidized enrollees held steady at $888 annually in 2024 and 2025 due to the enhanced premium tax credits).

Premium Payments in 2026 Will More than Double if ACA Enhanced Premium Tax Credits Expire (Grouped column chart)

The increase in premium payments with expiration of the enhanced premium tax credits is even higher than previously estimated for two reasons:

  • Trump administration changes to tax credit calculations, and
  • Rising 2026 premiums.

The Trump administration made changes to the way tax credits are calculated, which were finalized in the ACA Marketplace Integrity and Affordability rule. The required contribution levels that will be in place for 2026 if the enhanced tax credits are not renewed will be higher relative to the required contribution levels calculated under the original methodology based on rules in effect at the time. This means that enrollees are expected to pay a higher share of their income towards a benchmark premium plan in 2026 than they otherwise would have. Additionally, inflation in private insurance premiums has led to higher premium contribution levels than previously expected.

Additionally, insurers in the ACA Marketplace are proposing to raise their rates by a median of 18%. Fueled by rising health care costs and the expiration of the enhanced premium tax credits, insurers are proposing the largest rate increases in 2026 since 2018, the last time uncertainty over federal policy changes contributed to sharp premium increases. As premiums increase, the enhanced tax credits provide additional savings to enrollees that receive them. This means that middle-income enrollees, whose payment for a benchmark plan is currently capped at 8.5% of their income and will lose financial assistance altogether, will have to cover the cost of premium increases in addition to the amount their tax credits would have previously covered to keep their same plan.

Enrollees across the income spectrum can expect big increases in premium payments  

Annual Premium Payments Would Increase for Subsidized Enrollees by an Average of ,016 (114%) if Enhanced Premium Tax Credits Expire (Stacked column chart)

Enrollees with incomes above 400% of poverty will be subject to large increases in premium payments if enhanced premium tax credits expire. On average, a 60-year-old couple making $85,000 (or 402% FPL) would see yearly premium payments rise by over $22,600 in 2026, after accounting for an annual premium increase of 18%. This would bring the cost of a benchmark plan to about a quarter of this couple's annual income, up from 8.5%. Meanwhile, a 45-year-old earning $20,000 (or 128% FPL) in a non-Medicaid expansion state would see their premium payments for a benchmark plan rise from $0 to $420 per year, on average, from the loss of enhanced premium tax credits. About half (45%) of ACA Marketplace enrollees have incomes between 100-150% of poverty, about a fourth (28%) have incomes between 150-250% of poverty, and roughly 1 in 10 have incomes above 400% of poverty.

Methods

The average savings by income group for 2024 were taken from the 2024 Open Enrollment report. The average yearly premium savings from enhanced premium tax credits (ePTC) for enrollees under 400% FPL were defined as the sum of the differences between the required contribution amounts with and without ePTC, using the estimated percent of plan selections with ePTC by income category and assuming a uniform income distribution within each category. To extrapolate to 2026, income was inflated by the ratio of the 2025 federal poverty guidelines to the 2023 federal poverty guidelines for an individual in the continental US. For each income category, the savings were assumed to grow as the ratio of the savings between 2026 and 2024. Due to a provision in the reconciliation bill related to subsidized ACA Marketplace eligibility for immigrants, no enrollees under 100% FPL are assumed to receive premium tax credits in 2026 and are thus not included in the calculation of average savings. For enrollees at or above 400% FPL, savings were defined as difference between the average unsubsidized premium and 8.5% of the average individual income, the required contribution under the enhanced tax credits for enrollees in this income category. For 2026, the average unsubsidized premium was assumed to be 18% higher than the 2025 average unsubsidized premium, based on analysis of rate filings. Calculations assume that there are no changes in plan selection, family composition, income relative to FPL, and geography between 2024 and 2026. The annual premium payment for 2026 comprises the estimated savings from enhanced tax credits in 2026 and the average premium payment among subsidized enrollees in 2025 obtained from the 2025 Open Enrollment State-Level Public Use File. State-funded subsidies might offset some increases of premiums but are not accounted for in the estimation. Numbers from the Open Enrollment report for estimated consumer APTC savings due to the ARP and IRA by income category (Table 8) were reported as whole numbers; a Monte Carlo method was used to account for this rounding, keeping all observations that rounded to the grand mean listed in the report.