


A Current Snapshot of the Medicare Part D Prescription Drug Benefit

Published: Oct 7, 2025

Medicare Part D is a voluntary outpatient prescription drug benefit for people with Medicare provided through private plans that contract with the federal government. Beneficiaries can choose to enroll in either a stand-alone prescription drug plan (PDP) to supplement traditional Medicare or a Medicare Advantage drug plan (MA-PD) that includes drug coverage and all other Medicare-covered benefits. This brief provides an overview of the Medicare Part D program, plan availability, enrollment, and spending and financing, based on KFF analysis of data from the Centers for Medicare & Medicaid Services (CMS) and other sources. It also provides an overview of changes to the Part D benefit based on provisions in the Inflation Reduction Act. (A separate KFF analysis provides more detail about Part D plan availability, premiums, and cost sharing.)

Takeaways

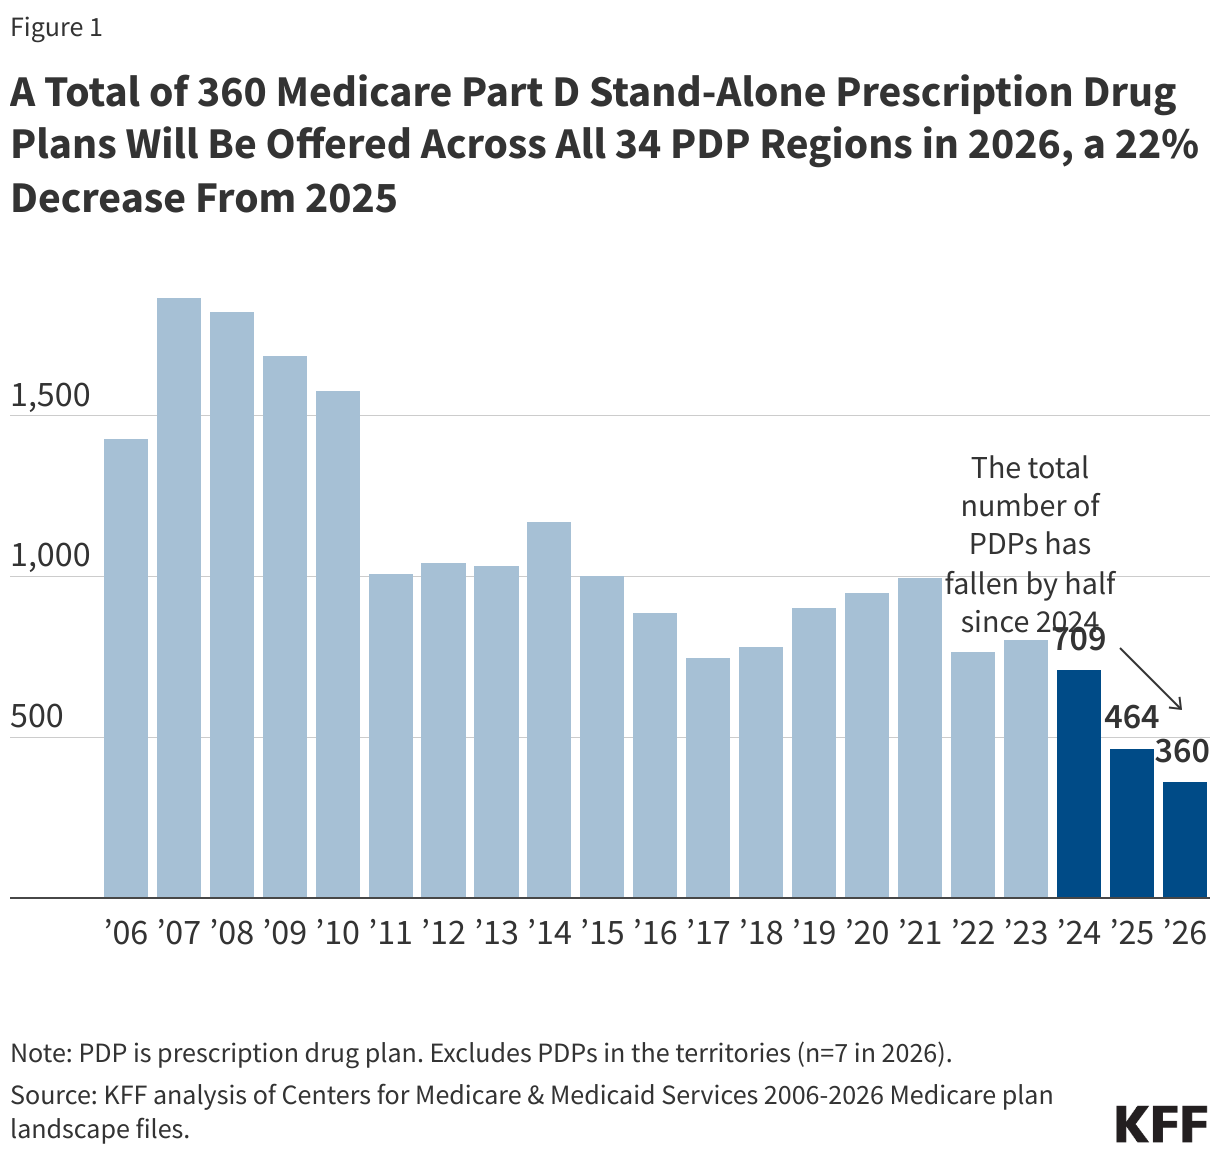
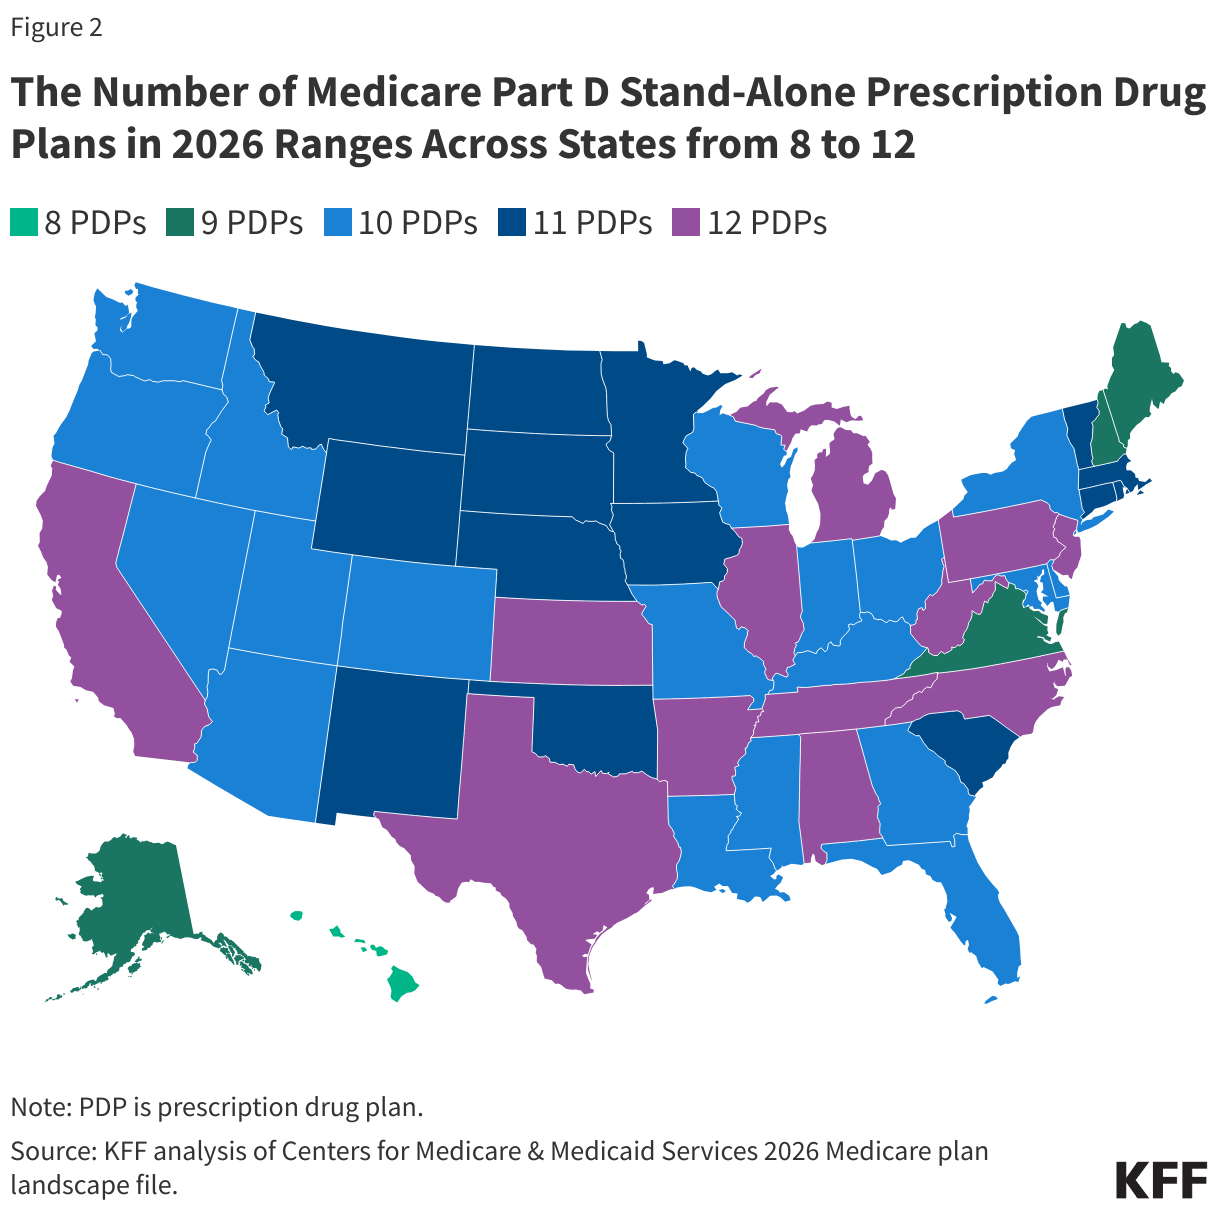
  • In 2026, beneficiaries in each state will have a choice of between 8 and 12 Medicare Part D stand-alone prescription drug plans, plus many Medicare Advantage drug plans. A total of 360 PDPs will be offered by 17 different parent organizations across the 34 PDP regions nationwide (excluding 7 PDPs in the territories), a 22% decrease in PDPs from 2025 and 2 fewer parent organizations.
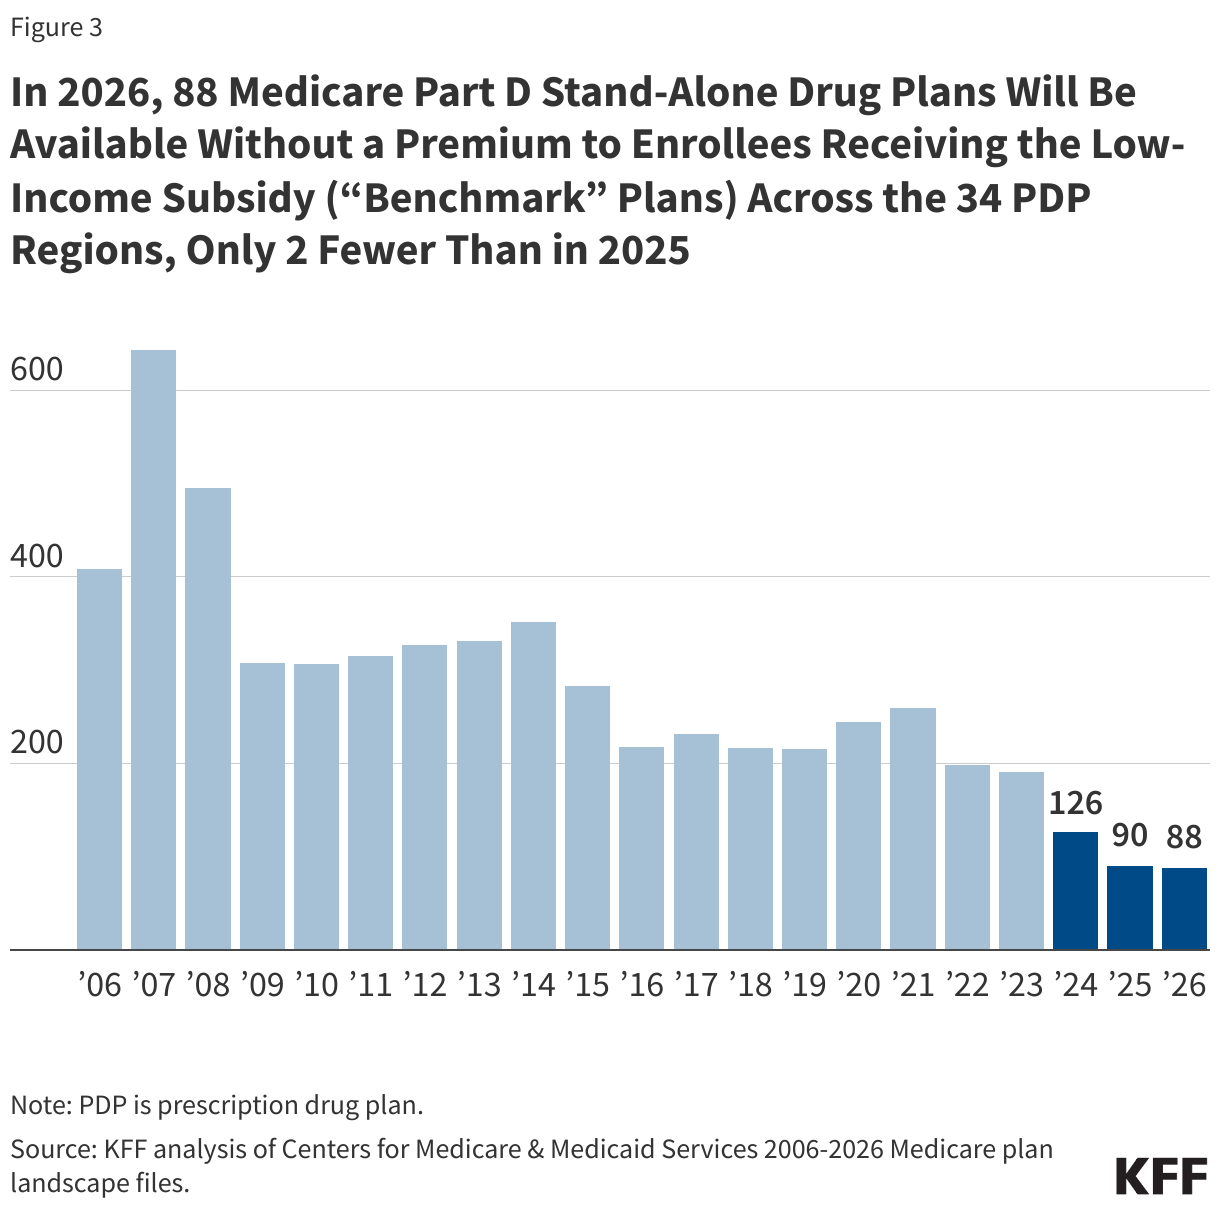
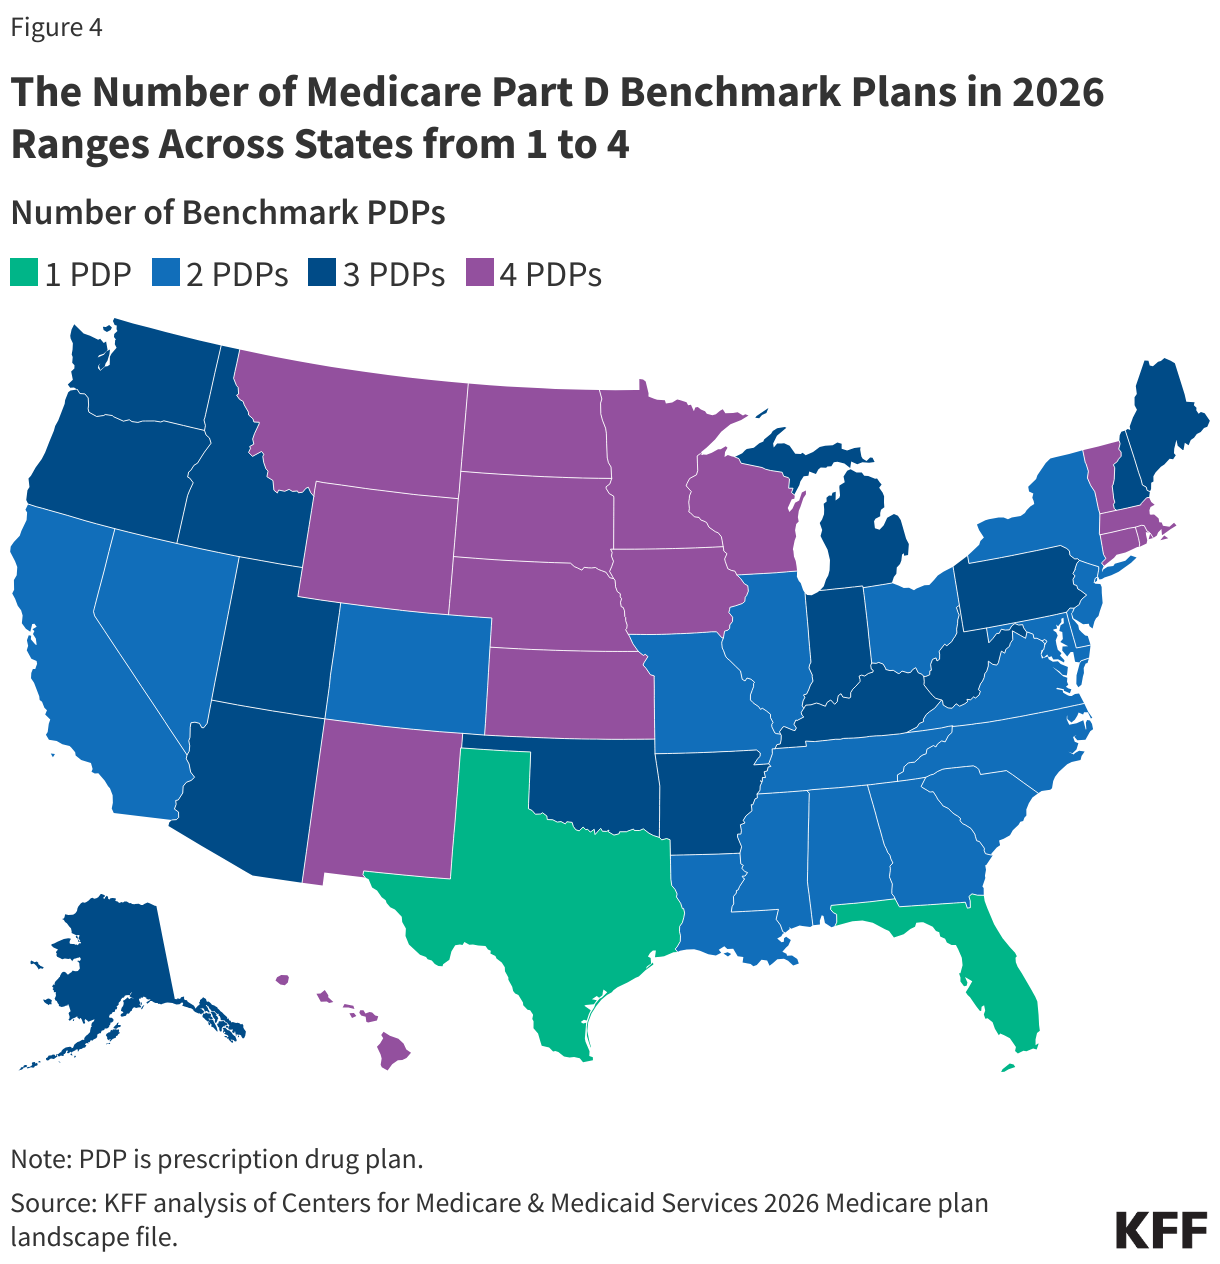
  • Roughly the same number of PDPs will be available for enrollment of Part D Low-Income Subsidy (LIS) beneficiaries for no premium (“benchmark” plans) in 2026, varying from 1 to 4 PDPs across states. A total of 88 PDPs will be benchmark plans in 2026, 2 fewer than in 2025.
  • Several changes to the Medicare Part D benefit under the Inflation Reduction Act have taken effect, including a cap on out-of-pocket drug spending, which will be set at $2,100 in 2026; an increase in the share of drug costs above the cap paid for by Part D plans and drug manufacturers; and a reduction in Medicare’s share of these costs.
  • In 2025, 54.8 million of the 68.8 million Medicare beneficiaries in total are enrolled in Medicare Part D plans, including employer-only group plans; among Part D enrollees, 58% are enrolled in MA-PDs and 42% are enrolled in stand-alone PDPs. As of May 2025, 13.9 million Part D enrollees receive premium and cost-sharing assistance through the LIS program.
  • Medicare’s actuaries estimate that spending on Part D benefits (net of premiums paid by enrollees) will total $140 billion in 2026, representing 11% of total spending on all Medicare-covered benefits. Funding for Part D comes from federal government contributions (75%), beneficiary premiums (13%), and state contributions (12%).
  • Medicare’s payments to Part D plans to subsidize the cost of basic Part D benefits per enrollee are projected to account for roughly three-fourths of Medicare’s total reimbursement per enrollee in 2026, while reinsurance payments (to subsidize a portion of drug spending for enrollees with high drug costs) will equal one-fourth. This is a reversal from 2024, when reinsurance accounted for three-fourths of total reimbursement per enrollee. This change reflects the increased generosity of the standard Part D benefit with the addition of an out-of-pocket spending cap in 2025, along with the reduction in Medicare’s liability for catastrophic drug costs from 80% in 2024 to 20% for brands and 40% for generics in 2025. Part D plans and drug manufacturers now bear greater responsibility for catastrophic coverage costs.

Medicare Prescription Drug Plan Availability in 2026

In 2026, a total of 360 PDPs will be offered by 17 different parent organizations across the 34 PDP regions nationwide (excluding the territories), a 22% decrease in PDPs from 2025 (and nearly half as many as in 2024) and 2 fewer parent organizations (Figure 1). While the availability of stand-alone PDPs has been trending downward over time, the availability of Medicare Advantage drug plans has expanded in recent years, and more people in Medicare are now getting Part D drug coverage through Medicare Advantage plans.

A Total of 360 Medicare Part D Stand-Alone Prescription Drug Plans Will Be Offered Across All 34 PDP Regions in 2026, a 22% Decrease From 2025 (Column Chart)

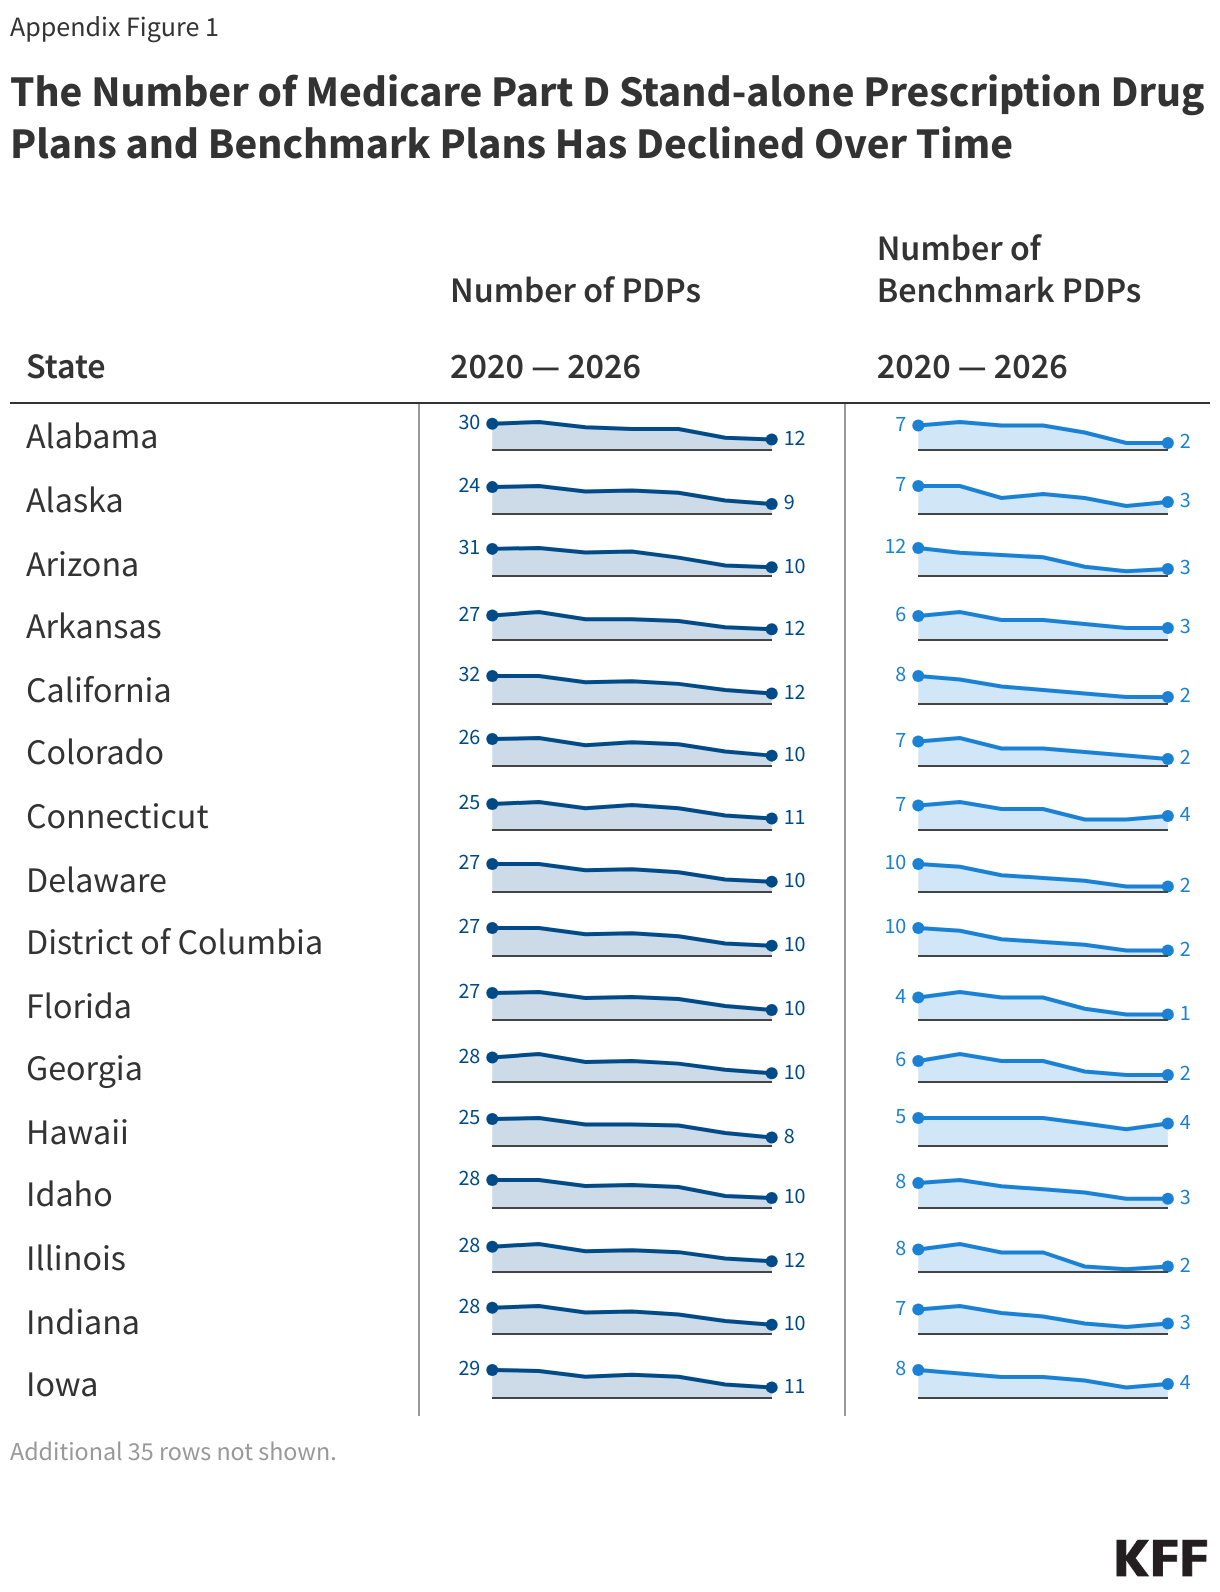
Despite a reduction in the number of PDPs overall, beneficiaries in each state will have a choice of between 8 and 12 stand-alone PDPs offered by between 4 and 6 parent organizations in each state (Figure 2, Appendix Figure 1). In addition, beneficiaries will be able to choose from among many MA-PDs available at the county level.

The Number of Medicare Part D Stand-Alone Prescription Drug Plans in 2026 Ranges Across States from 8 to 12 (Choropleth map)

Low-Income Subsidy Plan Availability in 2026

Beneficiaries with low incomes and modest assets are eligible for assistance (“extra help”) with Part D plan premiums and cost sharing. Through the Part D Low-Income Subsidy (LIS) program, additional premium and cost-sharing assistance is available for Part D enrollees with low incomes (less than 150% of poverty, or $23,475 for individuals/$31,725 for married couples in 2025) and modest assets (up to $17,600 for individuals/$35,1300 for couples in 2025). People who qualify for the LIS program pay modest copayments for prescription drugs, no drug deductible, and no premium for drug coverage in premium-free “benchmark” plans.

In 2026, roughly the same number of plans will be available for enrollment of LIS beneficiaries for no premium (benchmark plans) compared to 2025 – 88 plans (2 fewer than in 2025), but the lowest number of benchmark plans available since Part D started (Figure 3). Overall, one quarter (24%) of PDPs in 2026 are benchmark plans.

In 2026, 88 Medicare Part D Stand-Alone Drug Plans Will Be Available Without a Premium to Enrollees Receiving the Low-Income Subsidy (“Benchmark” Plans) Across the 34 PDP Regions, Only 2 Fewer Than in 2025 (Column Chart)

At the PDP region level, the number of PDP choices overall remains more robust than the number of premium-free benchmark PDPs. In 2026, the number of premium-free PDPs ranges across states from 1 plan in 2 states (Florida and Texas) to 4 plans in 15 states (Figure 4, Appendix Figure 1). LIS enrollees can select any plan offered in their area, but if they are enrolled in a non-benchmark plan, they may be required to pay some portion of their plan’s monthly premium.

The Number of Medicare Part D Benchmark Plans in 2026 Ranges Across States from 1 to 4 (Choropleth map)

Changes to Part D Under the Inflation Reduction Act

The Inflation Reduction Act of 2022 contained several provisions to lower prescription drug spending by Medicare and beneficiaries, including major changes to the Medicare Part D program, which started to take effect in 2023. These changes were designed to address several concerns, including the lack of a hard cap on out-of-pocket spending for Part D enrollees; the inability of the federal government to negotiate drug prices with manufacturers; a significant increase in Medicare “reinsurance” spending for Part D enrollees with high drug costs; prices for many Part D covered drugs rising faster than the rate of inflation; and the relatively weak financial incentives faced by Part D plan sponsors to control high drug costs. Provisions in the law include:

  • Limiting the price of insulin products to no more than $35 per month in all Part D plans and makes adult vaccines covered under Part D available for free, as of 2023.
  • Requiring drug manufacturers to pay a rebate to the federal government if prices for drugs covered under Part D and Part B increase faster than the rate of inflation, with the initial period for measuring Part D drug price increases running from October 2022-September 2023.
  • Expanding eligibility for full benefits under the Part D Low-Income Subsidy program in 2024.
  • Adding a hard cap on out-of-pocket drug spending under Part D by eliminating the 5% coinsurance requirement for catastrophic coverage in 2024 and capping out-of-pocket spending at $2,000 in 2025 (increasing to $2,100 in 2026).
  • Shifting more of the responsibility for catastrophic coverage costs to Part D plans and drug manufacturers, starting in 2025.
  • Authorizing the Secretary of the Department of Health and Human Services to negotiate the price of some drugs covered under Medicare, with negotiated prices first available for 10 Part D drugs in 2026.

Part D Plan Premiums and Benefits in 2026

Premiums

The 2026 Part D base beneficiary premium – which is based on bids submitted by both PDPs and MA-PDs and is not weighted by enrollment – is $38.99, a 6% increase from 2025. Annual growth in the base beneficiary premium is capped at 6% due to a provision in the Inflation Reduction Act. Because the base premium is an average across both types of plans and reflects the cost of basic benefits only, this amount does not equal what a Part D enrollee will pay for coverage in any given Part D plan.

Because the monthly amount that Part D enrollees pay for individual Part D plans is different from the base beneficiary premium, enrollees may see their premium increase by more or less than 6%, or even decrease, if they stay in the same plan for 2026. A Part D premium stabilization demonstration for PDPs is also helping to moderate premium increases that Part D enrollees might otherwise have faced in 2026, as insurers continue to adjust to higher costs associated with the new out-of-pocket spending cap and increased liability for drug costs above the cap. The Part D premium demonstration was established in 2024 by the Biden administration ahead of the major redesign of the Part D benefit that took effect in 2025. For the first year of the demonstration, the federal government provided participating PDPs with an across-the-board monthly premium subsidy of up to $15 and limited the monthly premium increase for 2025 to $35, along with a narrowing of the risk corridors to mitigate the risk of losses for participating PDPs. For 2026, the Trump administration reduced the monthly premium subsidy from $15 to $10, raised the limit on the PDP monthly premium increase to $50, and eliminated the risk corridor component of the demonstration.

Actual monthly premiums paid by Part D enrollees in stand-alone PDPs in 2026 will vary considerably, ranging from $0 to $100 or more in most regions. In addition to the monthly premium, Part D enrollees with higher incomes ($106,000/individual; $212,000/couple) pay an income-related premium surcharge, ranging from $13.70 to $85.80 per month in 2025 (depending on income).

Most MA-PD enrollees pay no premium beyond the monthly Part B premium (although high-income MA enrollees are required to pay a premium surcharge). MA-PD sponsors can use rebate dollars from Medicare payments to lower or eliminate their Part D premiums, so the average premium for drug coverage in MA-PDs is heavily weighted by zero-premium plans. In 2025, the enrollment-weighted average monthly portion of the premium for drug coverage in MA-PDs is substantially lower than the average monthly PDP premium ($7 versus $39).

Benefits

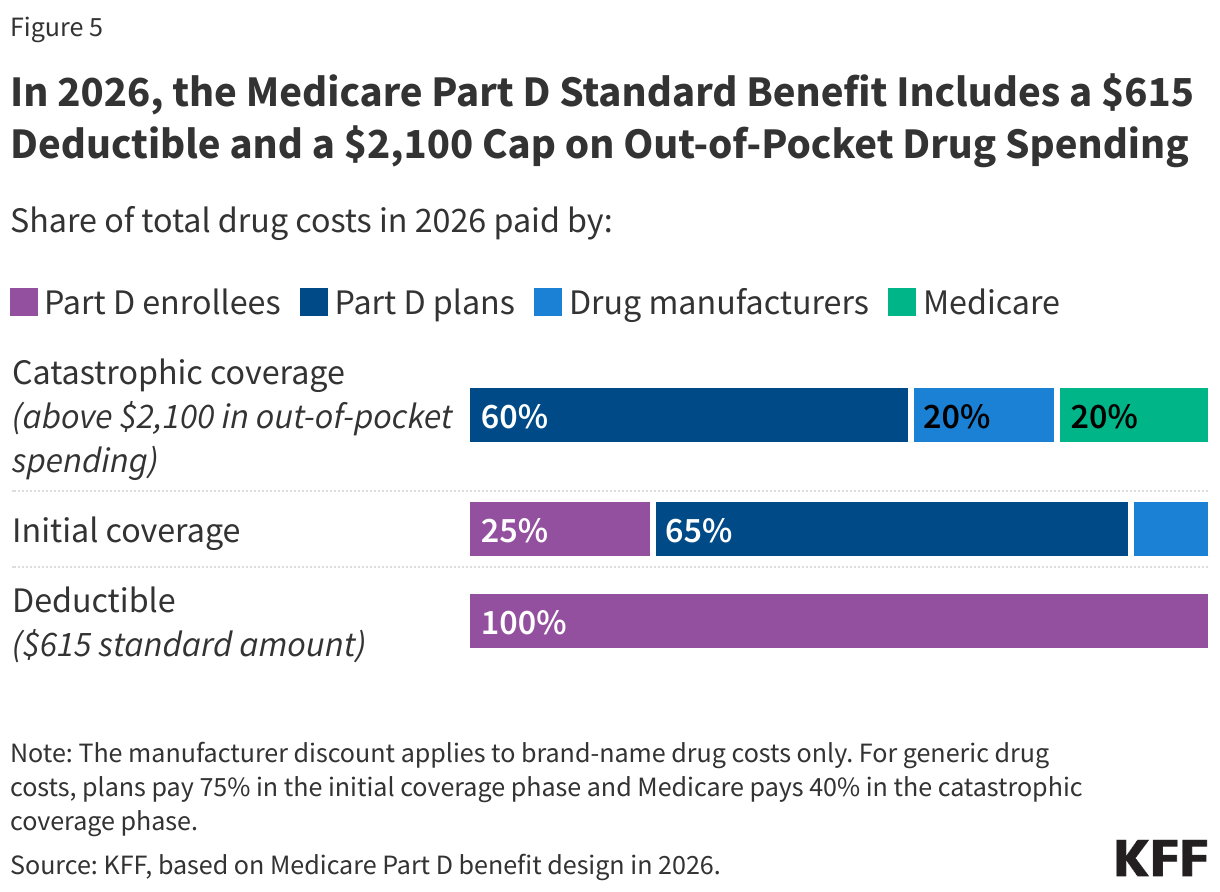
The Part D defined standard benefit changed substantially in 2025 and now includes a cap on out-of-pocket drug spending. The benefit has three phases, including a deductible, an initial coverage phase, and catastrophic coverage. For 2026, under the standard benefit, Part D enrollees will pay a deductible of $615 (up from $590 in 2024), and will then pay 25% of their drug costs in the initial coverage phase until their out-of-pocket spending totals $2,100 (Figure 5). At that point, they qualify for catastrophic coverage and pay no additional out-of-pocket costs.

In 2026, the Medicare Part D Standard Benefit Includes a 5 Deductible and a ,100 Cap on Out-of-Pocket Drug Spending (Stacked Bars)

Part D plans must offer either the defined standard benefit or an alternative equal in value (“actuarially equivalent”) and can also provide enhanced benefits. Both basic and enhanced benefit plans vary in terms of their specific benefit design, coverage, and costs, including deductibles, cost-sharing amounts, utilization management tools (i.e., prior authorization, quantity limits, and step therapy), and which drugs are covered on their formularies. Plan formularies must include drug classes covering all disease states, and a minimum of two chemically distinct drugs in each class. Part D plans are required to cover all drugs in six “protected” classes: immunosuppressants, antidepressants, antipsychotics, anticonvulsants, antiretrovirals, and antineoplastics.

Part D plans are also required to cover all drugs that have been selected for Medicare drug price negotiation, including all dosage forms and strengths. CMS will use the annual formulary review process to ensure that all Part D plans cover all dosages and formulations of selected drugs. Negotiated prices for the first 10 drugs that were selected for negotiation will take effect for Medicare beneficiaries on January 1, 2026.

Part D and Low-Income Subsidy Enrollment in PDPs and MA-PDs

Enrollment in Medicare Part D plans is voluntary, except for beneficiaries who are eligible for both Medicare and Medicaid and certain other low-income beneficiaries who are automatically enrolled in a PDP if they do not choose a plan on their own. Beneficiaries face a penalty equal to 1% of the national average premium for each month they delay enrollment unless they have drug coverage from another source that is at least as good as standard Part D coverage (“creditable coverage”).

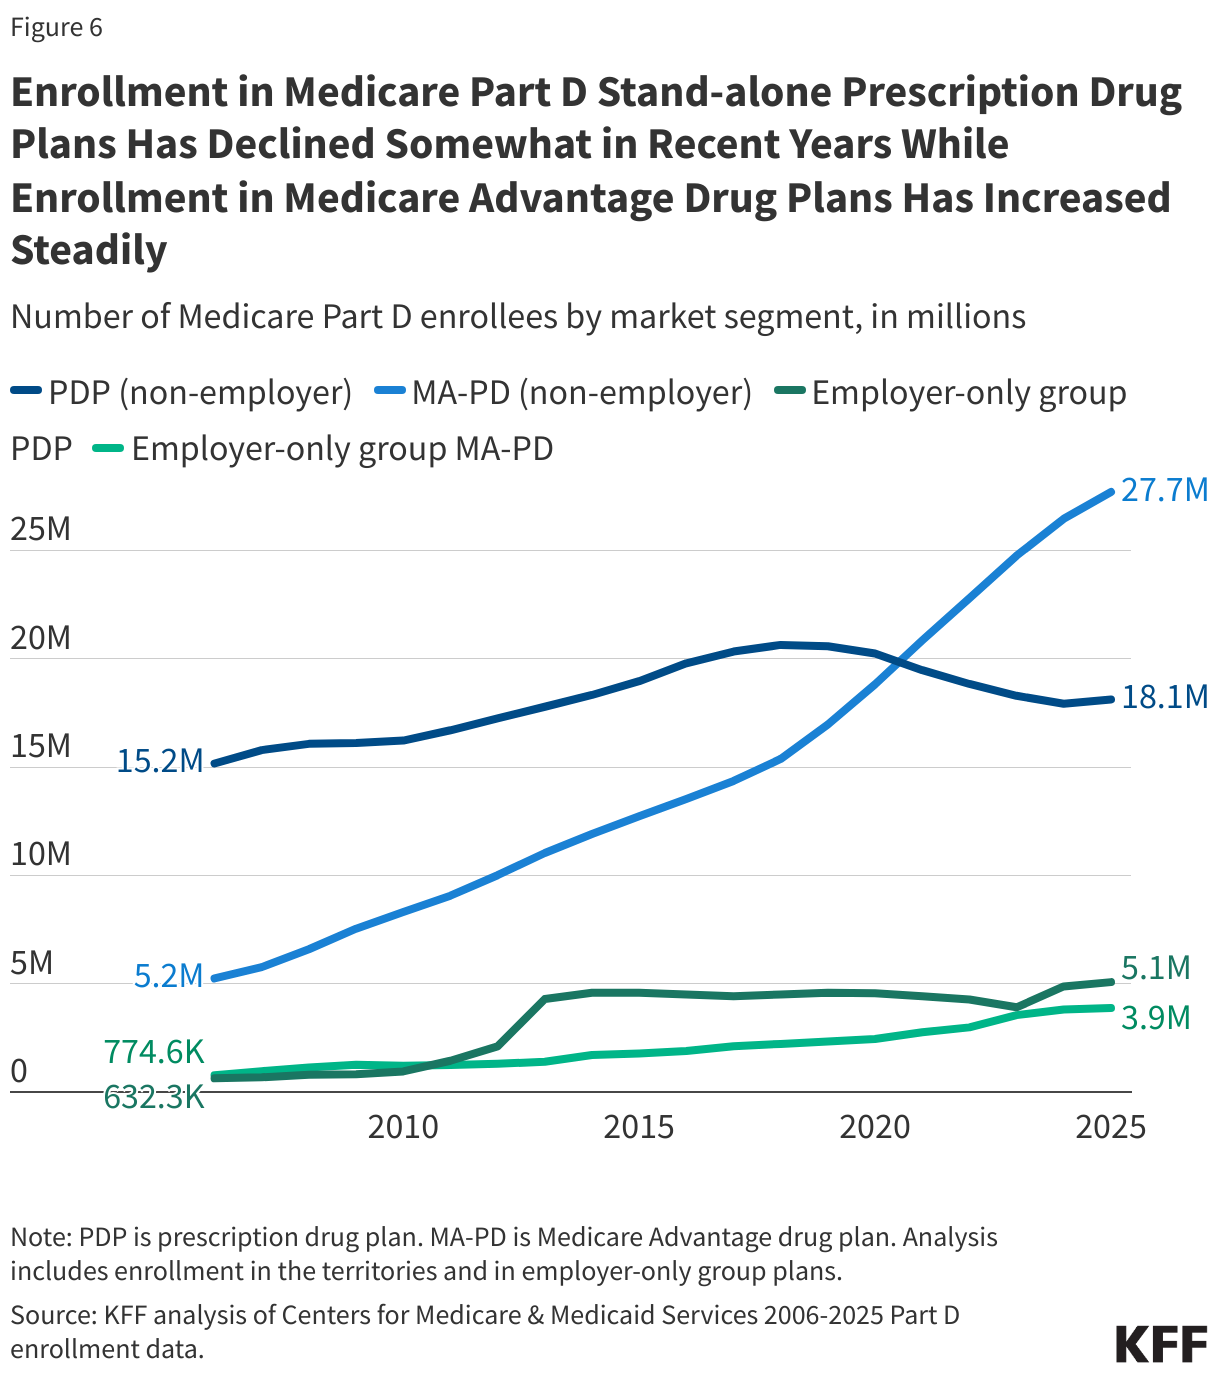
In 2025, 54.8 million Medicare beneficiaries are enrolled in Medicare Part D plans, including employer-only group plans; of the total, 58% are enrolled in MA-PDs and 42% are enrolled in stand-alone PDPs (Figure 6). Another 0.7 million beneficiaries are estimated to have drug coverage through employer-sponsored retiree plans where the employer receives a subsidy from the federal government equal to 28% of drug expenses between $615 and $12,650 per retiree in 2026. Several million beneficiaries are estimated to have other sources of drug coverage, including employer plans for active workers, FEHBP, TRICARE, and Veterans Affairs (VA). Around 11% of people with Medicare are estimated to lack creditable drug coverage.

Enrollment in Medicare Part D Stand-alone Prescription Drug Plans Has Declined Somewhat in Recent Years While Enrollment in Medicare Advantage Drug Plans Has Increased Steadily (Line chart)

Recent years have seen a growing divide in the Part D plan market between stand-alone PDPs, where the number of plans has generally been trending downward over time in conjunction with a reduction in PDP enrollment, and MA-PDs, where plan availability and enrollment have grown steadily in recent years. The widespread availability of low or zero-premium MA-PDs, while PDPs charge substantially higher premiums on average, could tilt enrollment even more towards Medicare Advantage plans in the future.

As of May 2025, 13.9 million Part D enrollees receive premium and cost-sharing assistance through the LIS program. As with overall Part D enrollment, more LIS enrollees are in MA-PDs than PDPs. Beneficiaries who are dual-eligible individuals, those enrolled in Medicare Savings Programs (QMBs, SLMBs, QIs), and those who receive Supplemental Security Income payments from Social Security automatically qualify for the additional assistance, and they are automatically enrolled in PDPs with premiums at or below the regional Low-Income Subsidy benchmark premium amount if they do not choose a plan on their own. Other beneficiaries can apply for the Low-Income Subsidy through either the Social Security Administration or Medicaid and are subject to both an income and asset test. 

Part D Spending and Financing

Part D Spending

Medicare’s actuaries estimate that spending on Part D benefits (net of premiums paid by enrollees) will total $141 billion in 2026, representing 11% of total Medicare benefits spending.

In general, Part D spending depends on several factors, including the total number of Part D enrollees, their health status and the quantity and type of drugs used, the number of high-cost enrollees (those with drug spending above the catastrophic threshold), the number of enrollees receiving the Low-Income Subsidy, the price of drugs covered by Part D and the ability of plan sponsors to negotiate discounts (rebates) with drug companies and preferred pricing arrangements with pharmacies, and to manage use (e.g., promoting use of generic drugs, prior authorization, step therapy, quantity limits, and mail order). Part D spending is also affected by the level of price discounts that the federal government negotiates under the Medicare Drug Price Negotiation Program, as well as the effect of the inflation rebate provision of the IRA on price growth for existing drugs and launch prices for new drugs.

Part D Financing

Financing for Part D comes from federal government contributions (75%), beneficiary premiums (13%), and state contributions (12%). Medicare subsidizes 74.5% of basic Part D benefit costs through a monthly capitated payment to Part D plans for each enrollee, based on an average of bids submitted by plans for their expected basic benefit costs, though this share may be higher with the Inflation Reduction Act’s 6% base beneficiary premium cap and the temporary Part D premium stabilization program in effect. Enrollee premiums for basic benefits were initially set to cover 25.5% of the cost of standard (basic) drug coverage, but with premium stabilization measures in effect, enrollees are paying a lower share of costs overall. Higher-income Part D enrollees pay a larger share of standard Part D costs, ranging from 35% to 85%, depending on income.

Payments to Plans

For 2026, Medicare’s actuaries estimate that Part D plans will receive direct subsidy payments from the federal government for the cost of basic Part D benefits (plus administrative expenses and profits) that average $1,710 per enrollee overall, $522 in reinsurance payments for very high-cost enrollees, and $1,337 in subsidy payments for enrollees receiving the LIS. Employers are expected to receive, on average, $561 in federal subsidies for retirees in employer-subsidy Part D plans. Part D plans also receive additional risk-adjusted payments based on the health status of their enrollees, and plans’ potential total losses or gains are limited by risk-sharing arrangements with the federal government (“risk corridors”).

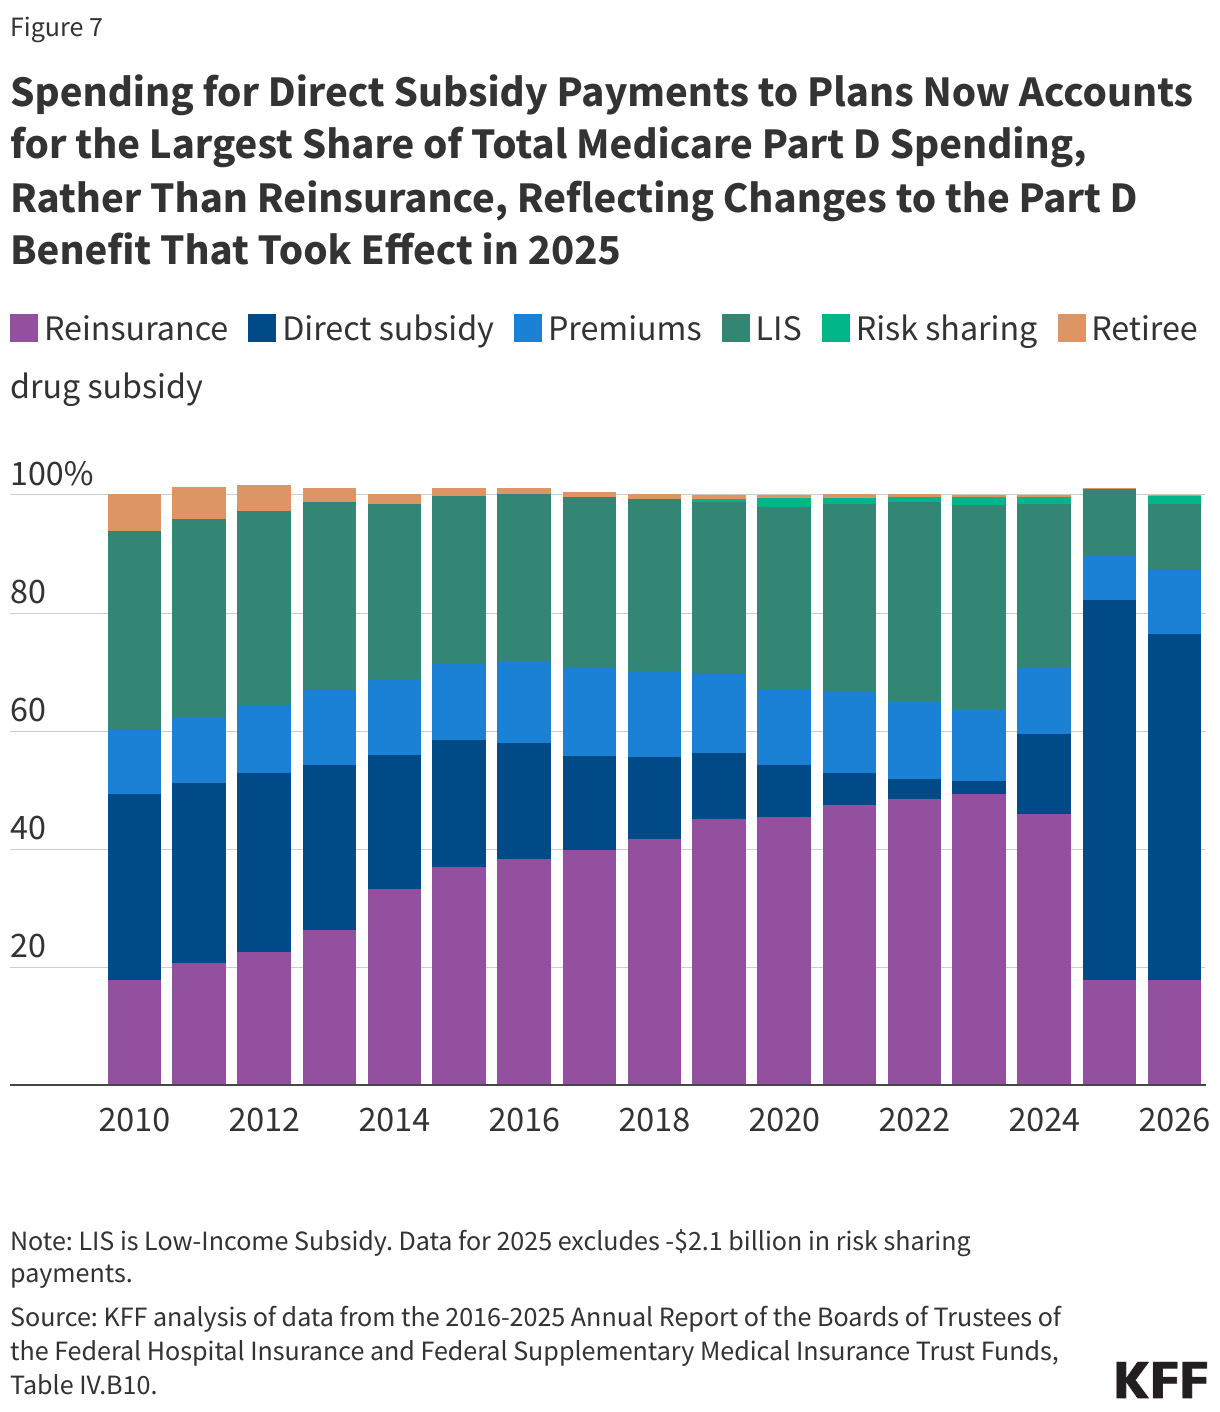
As of 2025, Medicare’s reinsurance payments to plans for total spending incurred by Part D enrollees above the catastrophic coverage threshold subsidize 20% of brand-name drug spending and 40% of generic drug spending, down from 80% in previous years, due to a provision in the Inflation Reduction Act. With this change in effect, Medicare's aggregate reinsurance payments to Part D plans are projected to account for 18% of total Part D spending in 2026, based on KFF analysis of data from the 2025 Medicare Trustees report. This is a substantial reduction from 2024, when reinsurance spending had grown to account for close to half of total Part D spending (46%) (Figure 7). Currently, the largest portion of total Part D spending is accounted for by direct subsidy payments to plans (59% of total spending in 2026).

Spending for Direct Subsidy Payments to Plans Now Accounts for the Largest Share of Total Medicare Part D Spending, Rather Than Reinsurance, Reflecting Changes to the Part D Benefit That Took Effect in 2025 (Stacked column chart)

Appendix

The Number of Medicare Part D Stand-alone Prescription Drug Plans and Benchmark Plans Has Declined Over Time (Table)

Medicare Part D Premiums Are Decreasing for Many Stand-Alone Drug Plans in a Number of States in 2026

Few Plans Are Increasing Premiums by $50, the Maximum Allowed Under the PDP Premium Stabilization Demonstration

Published: Oct 7, 2025

CMS has just released information about Medicare Part D plans for 2026, including plan availability and premiums for the coming year. As this year’s Medicare open enrollment period approaches, there’s some good news for Medicare Part D enrollees when it comes to monthly PDP premiums – lower on average, according to CMS – even as the total number of PDPs available drops yet again.

The headline of CMS’s press release emphasized stability in the Part D marketplace, but a quick review of the data shows that the total number of stand-alone drug plans available in 2026 will fall for the third year in a row, as plan sponsors scale back their PDP offerings (for example, Centene is discontinuing one of the 3 Wellcare PDP options; Health Care Service Corporation is discontinuing one of the 3 Cigna PDP options and withdrawing from several PDP regions) or exit the market entirely (as in the case of Elevance’s Anthem PDPs). Overall, there will be fewer PDPs in 2026 than in 2025 – 360 plans nationwide, down from 464 in 2025.

Firm decisions to exit the PDP market or scale back their PDP offerings in recent years have been based on evaluations about the profitability and viability of the stand-alone drug plan market, particularly for insurers with a smaller footprint, accounting for higher costs associated with a redesigned Part D benefit under the Inflation Reduction Act. The law added an out-of-pocket spending cap for Part D enrollees beginning in 2025 and shifted more of the share of high-drug cost enrollees from the federal government to the plans themselves, which increased plan liability overall. In addition, many insurers that offer both PDP and MA-PD plans have stated their interest in focusing resources on more lucrative Medicare Advantage markets.

Somewhat more unexpected than the reduction in plan availability for 2026 are the year-over-year premium changes for PDPs. A comprehensive KFF analysis will follow in the future, but it appears that substantial premium increases for PDPs across the board didn’t materialize, even as the Trump administration scaled back the level of support for additional PDP premium subsidies through the temporary Part D premium stabilization demonstration established by the Biden administration in 2024. For 2026, the federal government is providing participating PDPs with an across-the-board monthly premium subsidy of up to $10 (down from $15 in 2025) and limiting the monthly premium increase for 2026 to $50 (up from $35 in 2025) – revised parameters which, when they were announced, seemed to point in the direction of higher premiums for PDP coverage in 2026.

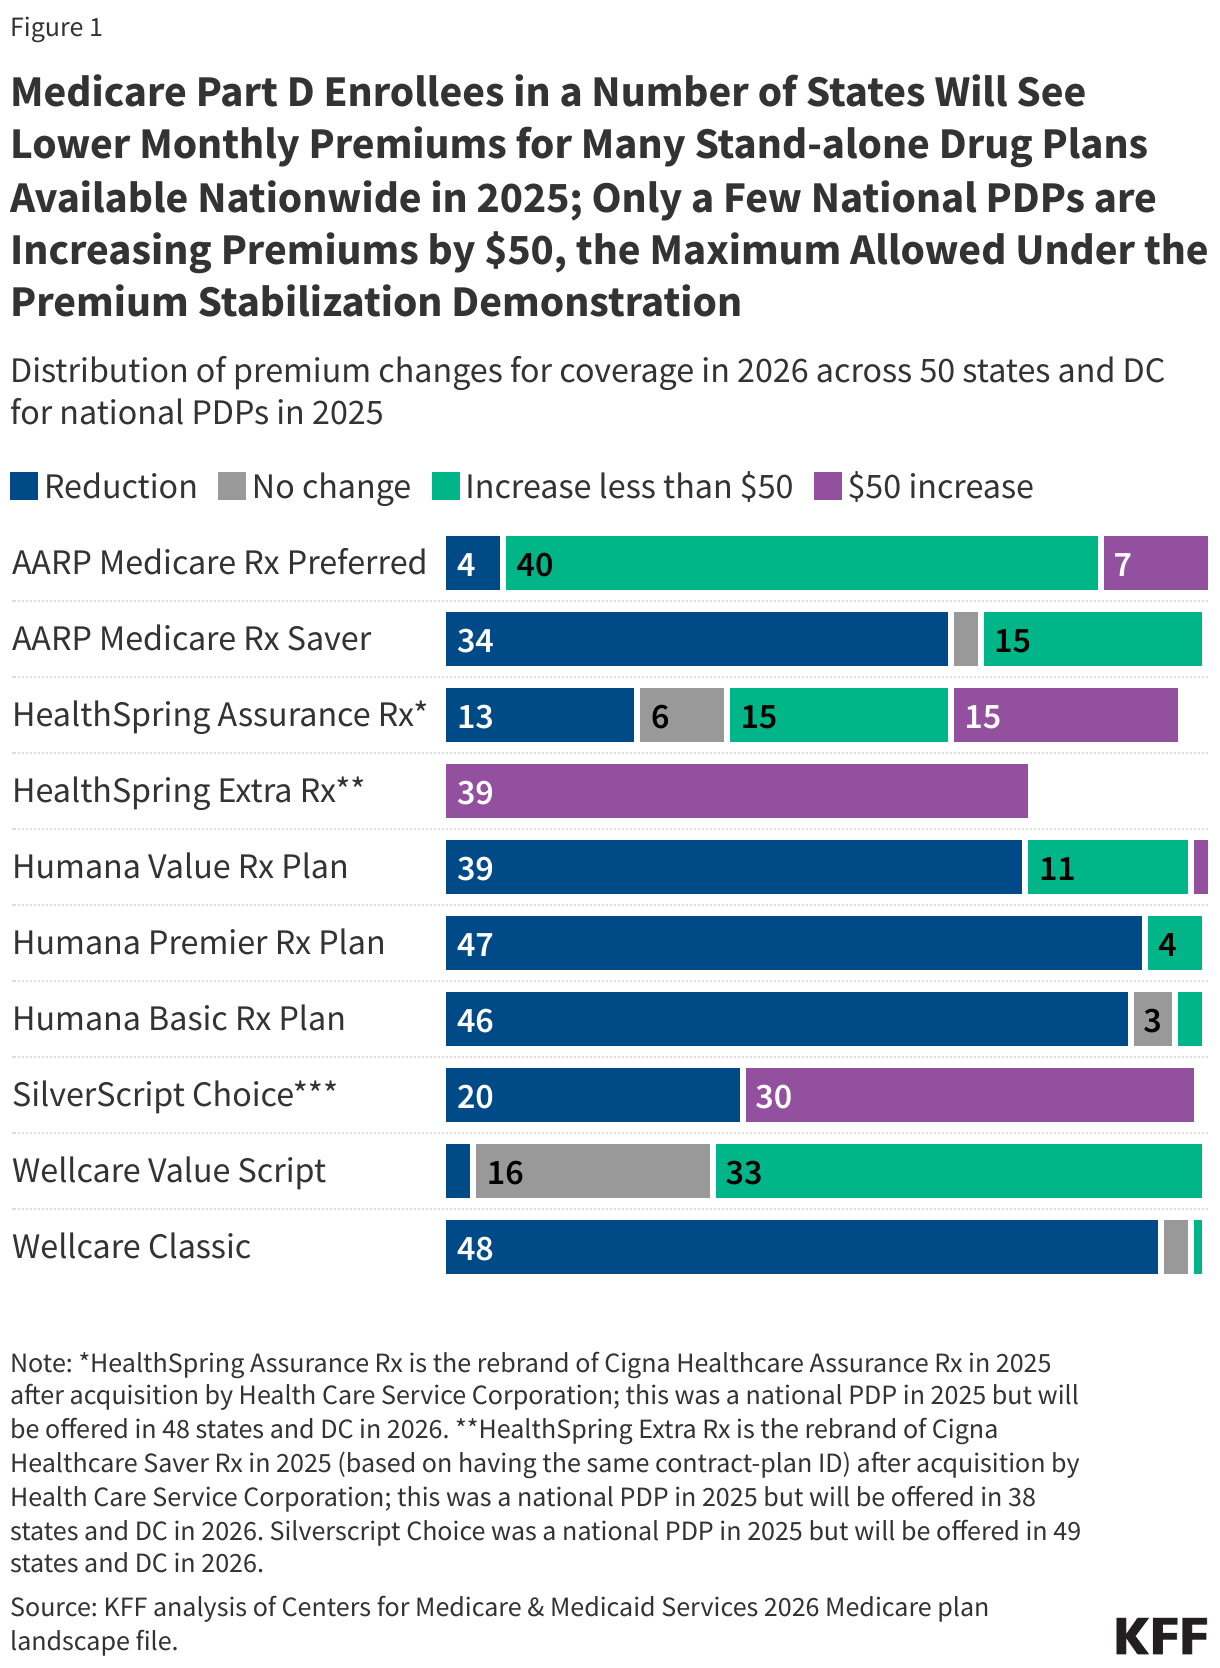
In fact, for all but one of the 10 PDPs that were offered nationwide in 2025 and that will continue to be offered on a national or near-national basis in 2026, Medicare Part D enrollees in a number of states will see lower monthly premiums in 2026 than in 2025. This is consistent with CMS’s projection that the average monthly PDP premium will decrease by a few dollars in 2026. Only a few national PDPs are increasing monthly premiums by $50, the maximum allowed under the premium stabilization demonstration, and PDP enrollees may have up to 6 PDPs available for $0 premium, depending on where they live.

Medicare Part D Enrollees in a Number of States Will See Lower Monthly Premiums for Many Stand-alone Drug Plans Available Nationwide in 2025; Only a Few National PDPs are Increasing Premiums by , the Maximum Allowed Under the Premium Stabilization Demonstration (Stacked Bars)

Looking at premium changes for a few of the more popular plans shows a mixed picture, however, with wide variation in monthly premiums across plans and the 50 states and DC (Figure 1):

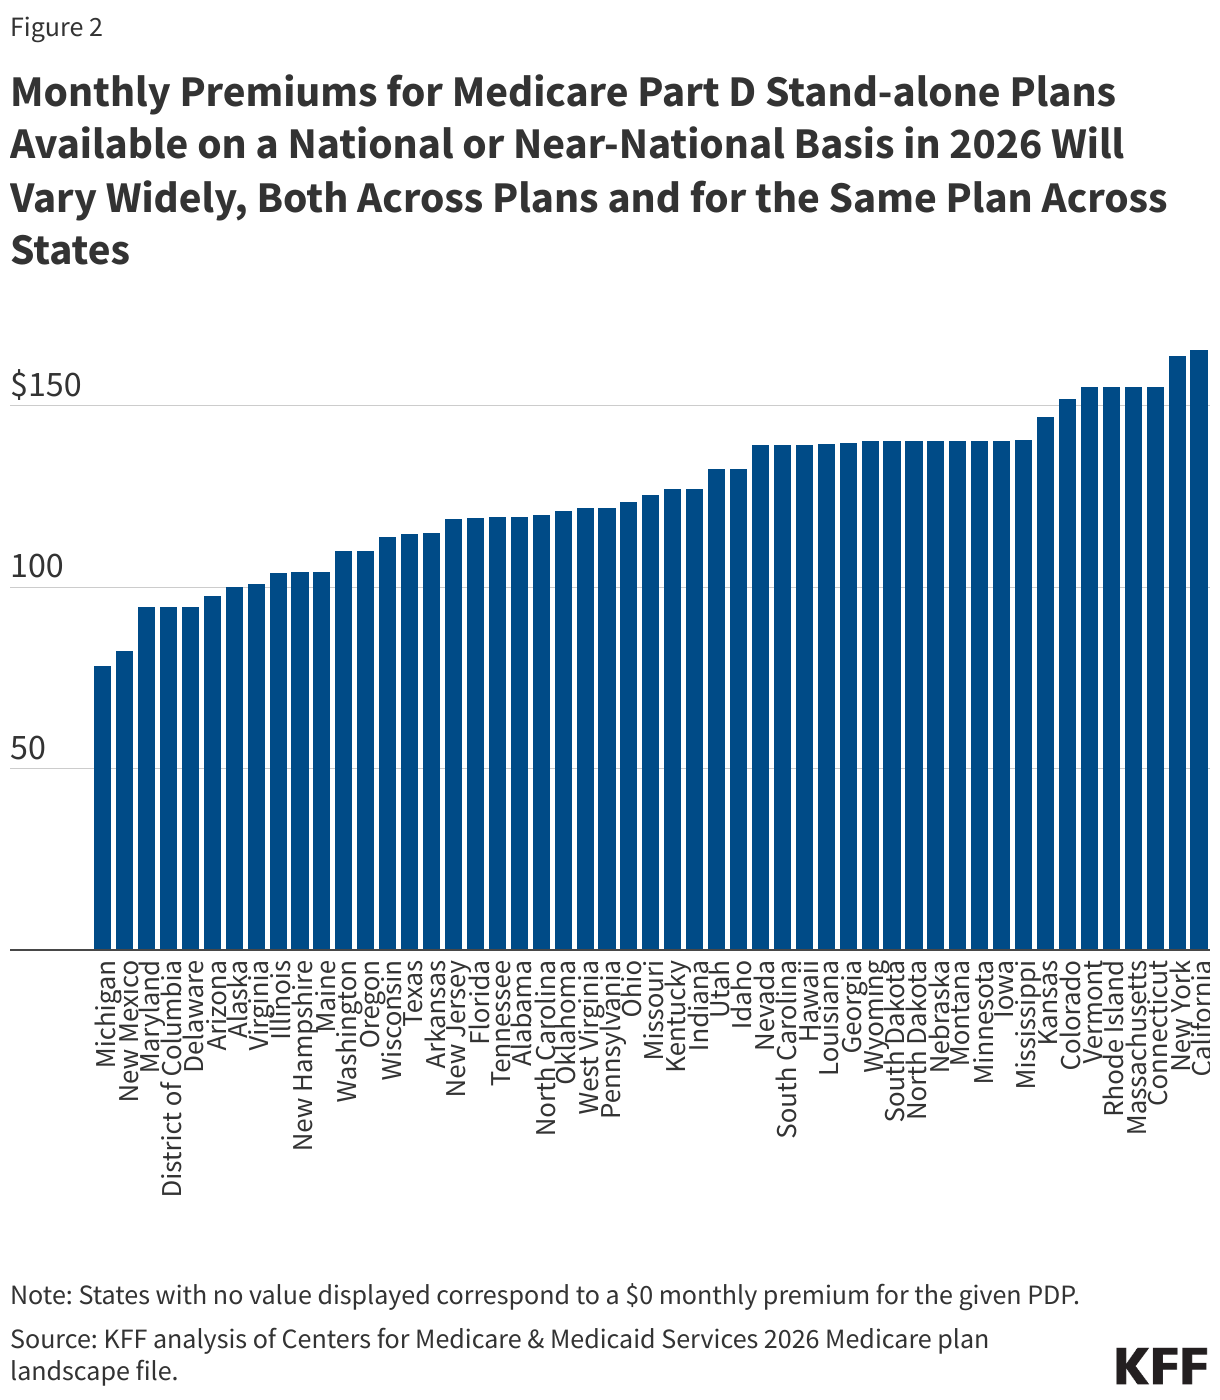
  • The monthly premium for the most popular PDP nationally, Wellcare Value Script, is increasing in more states (33, including DC) than where it is holding steady (16) or decreasing (2), and will range from $0 to $42.40 across states and DC in 2026 (Figure 2).
  • Enrollees in the second most popular PDP, Wellcare Classic, will see a premium reduction in 48 states (including DC), no change in 2, and an increase of less than $50 in 1. Monthly premiums will range from $0 to $45.70 across states and DC in 2026.
  • Enrollees in the third most popular PDP, SilverScript Choice, will face the maximum $50 increase in their monthly premium in 30 states (including DC), but a premium reduction in 20 other states. The monthly premium will vary across states and DC from $14.70 to $116.
Monthly Premiums for Medicare Part D Stand-alone Plans Available on a National or Near-National Basis in 2026 Will Vary Widely, Both Across Plans and for the Same Plan Across States (Column Chart)

According to CMS, virtually all PDP enrollees are in plans sponsored by insurers that opted to participate in the voluntary demonstration for 2026. In the absence of this demonstration and CMS’s actions during the bidding cycle for 2026 to negotiate and even reject plan bids, PDP premium increases would likely have been larger. And with 58% of all Part D enrollees in Medicare Advantage drug plans in 2025 and 42% in stand-alone PDPs, most Part D enrollees are not likely to face premium increases of any magnitude. This is because Medicare Advantage plans can use rebate dollars from the federal government to reduce premiums for prescription drug coverage. According to CMS, Medicare Advantage drug plan premiums for 2026 are holding steady at considerably lower levels than stand-alone drug plans, on average, with many plans charging zero premium for drug coverage in 2026, as in previous years.

Even if the monthly premium for a given Part D plan isn’t increasing, or is even decreasing, premiums are only one part of the story when it comes to Part D coverage. As is commonly advised during open enrollment, Medicare beneficiaries may want to look beneath the hood to see what other Part D plan features may be changing, including what drugs are and aren’t covered on the plan’s formulary, tier placement of covered drugs, deductibles, and cost-sharing requirements. The tradeoff with a reduction in premiums is that drug coverage may be getting less generous, which could mean fewer drugs covered, higher cost-sharing requirements, or greater utilization management restrictions – or likely some combination of all three.

A Look at Variation in Medicaid Spending Per Enrollee by Group and Across States

Published: Oct 6, 2025

Editorial Note

Originally published in August 2024, this data note was updated on October 6, 2025 with data from 2023, the most current Medicaid data available at the time of this analysis.

Medicaid is the primary program providing comprehensive health and long-term care coverage to approximately one in five low-income Americans. States administer Medicaid programs within broad federal rules, but have flexibility in designing programs, which creates variation in spending and enrollment as well as spending per enrollee across eligibility groups and states.

Over the coming years, state Medicaid programs may see significant reductions to their Medicaid enrollment and spending, resulting in changes to their spending per enrollee, across eligibility groups due to the recently enacted budget reconciliation package once called the “One Big, Beautiful Bill,” signed by President Trump on July 4th. The new law is estimated by the Congressional Budget Office (CBO) to cut federal Medicaid spending by $911 billion – or 14% of federal Medicaid spending – over the next ten years and increase the uninsured rate by 10 million, with some of the increase attributed to individuals losing Medicaid coverage. Provisions in the new law will have different effects on Medicaid spending and enrollment across the states. For example, over half of the reductions in federal spending (associated with most of the projected enrollment declines) stem from policies that only would affect states that have expanded Medicaid under the Affordable Care Act (ACA). How states respond to reductions in federal funding will impact the amount of spending reductions and the distribution of enrollment losses, which will affect Medicaid’s spending per enrollee. 

This data note provides an overview of total Medicaid (state and federal shares) spending per enrollee for full-benefit Medicaid enrollees by eligibility group and state in 2023. Data from 2023 are the most current Medicaid data available at the time of this analysis. Full-benefit Medicaid enrollees are those that qualify for a full range of Medicaid services such as doctor’s visits, hospitalizations, prescription drugs, and home health services. A small number of total enrollees (8% of all enrollees in 2023) qualify for only a limited set of Medicaid benefits such as family planning or treatment of an emergency medical condition and are not included in this analysis. References to Medicaid enrollees in this data note refer to full-benefit enrollees. See methods for more details. Detailed state-level data are also available on State Health Facts.

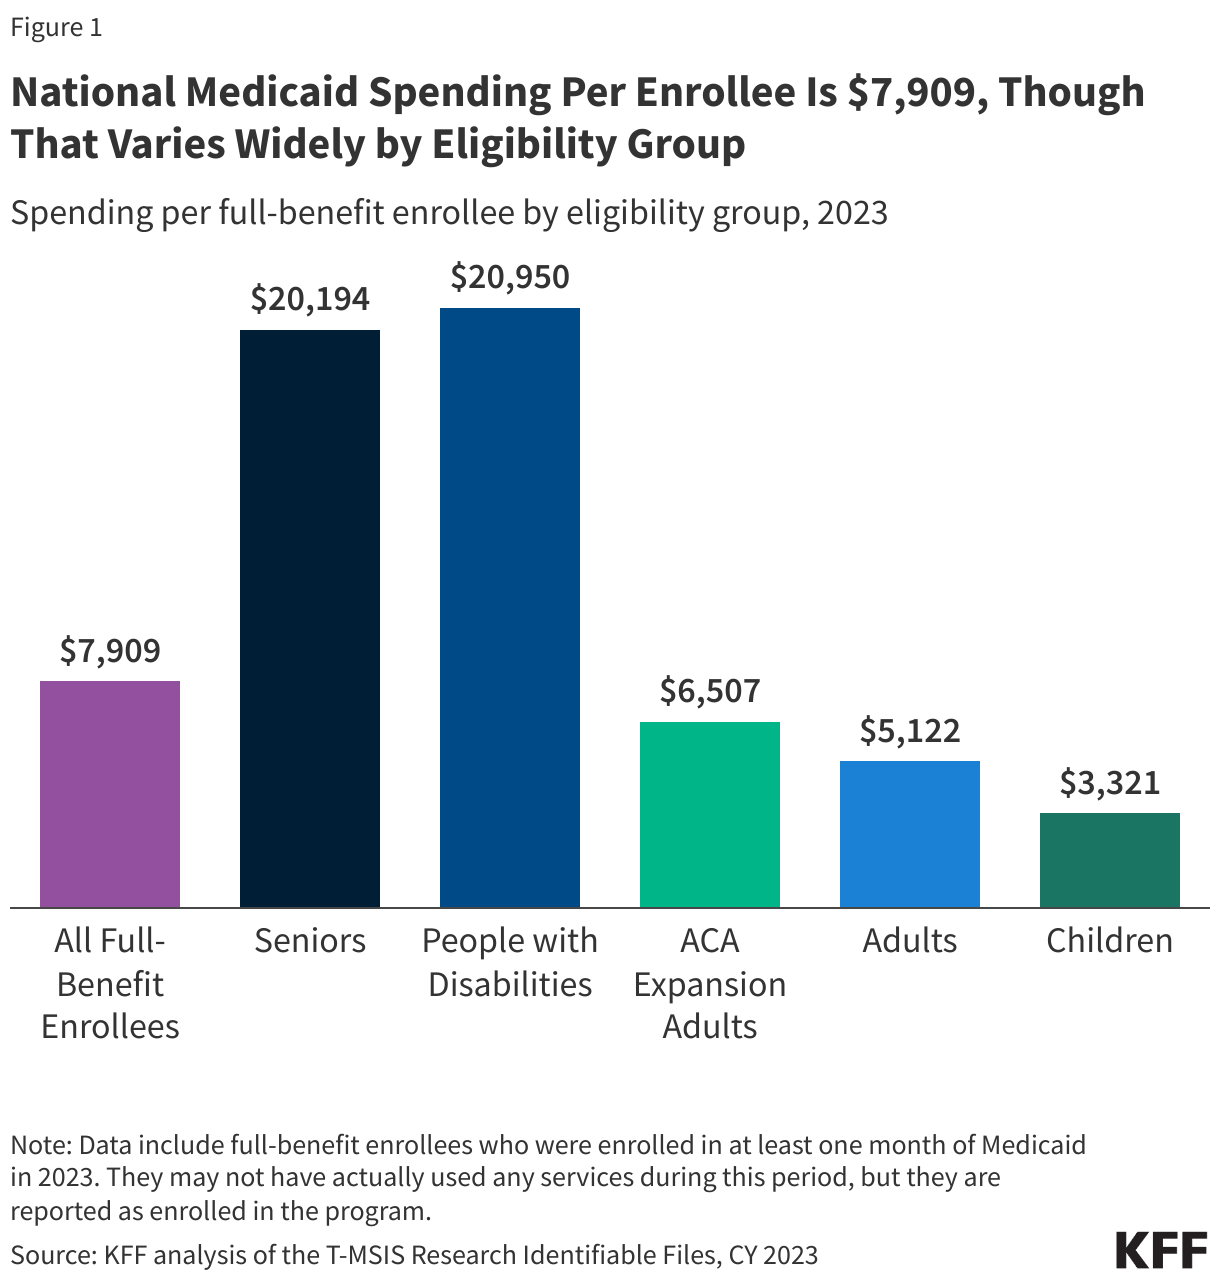
National Medicaid spending per enrollee is $7,909, though that varies widely by eligibility group (Figure 1). 

Overall, children account for 35% of full-benefit enrollment, but 15% of the spending, while adults ages 65 and older and people eligible because of a disability account for 19% of enrollment but 51% of the spending (data not shown). The disproportionate spending on certain eligibility groups stems from variation in spending per enrollee across the eligibility groups. Spending per enrollee is highest for people with disabilities ($20,950), and older adults ($20,194) (Figure 1). Those groups have per-enrollee spending approximately six times higher than child enrollees ($3,321), which have the lowest spending of any eligibility group (Figure 1). Differences in spending per enrollee reflect differences in health care needs and utilization. For example, older adults and people eligible on the basis of disability tend to have higher rates of chronic conditions, more complex health care needs and are more likely to utilize long-term care (LTC) than other enrollees. Most older adults and people with disabilities enrolled in Medicaid are also dually eligible for Medicare. For dual-eligible individuals, Medicare is the primary payer for acute care services while Medicaid pays for services that Medicare does not, including vision, dental, and most LTC. Medicaid spending per enrollee accounts for less than half of all spending for full-benefit dual-eligible individuals that are 65 and older.

National Medicaid Spending Per Enrollee Is ,909, Though That Varies Widely by Eligibility Group (Column Chart)

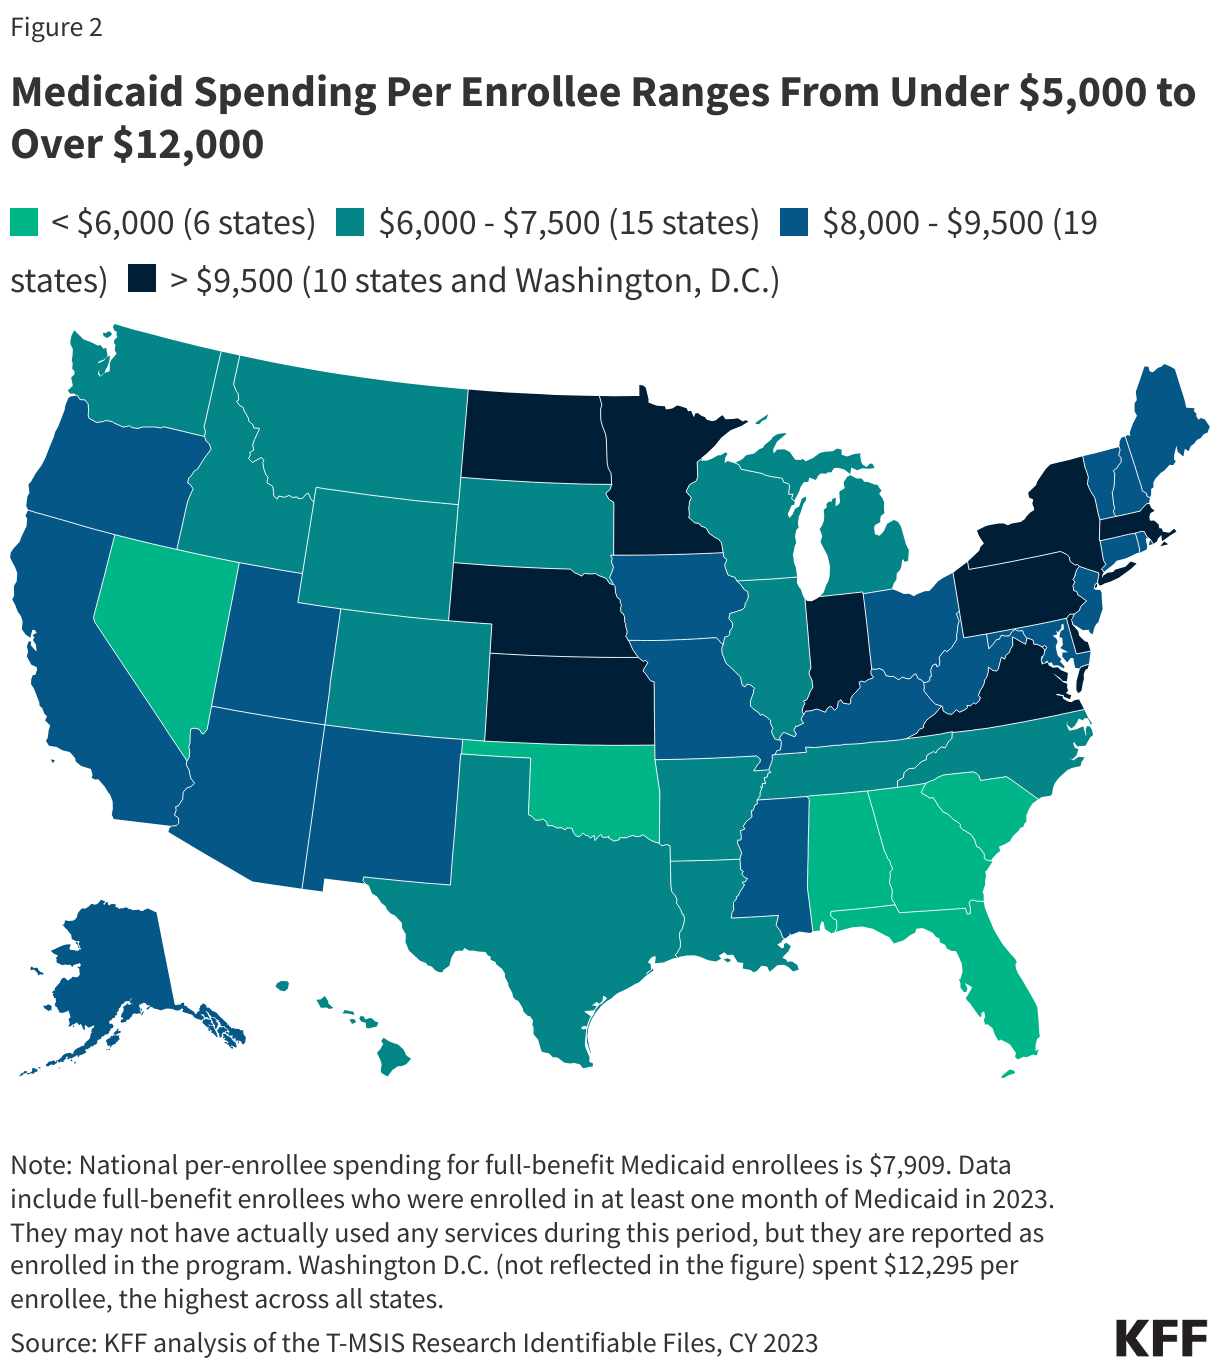
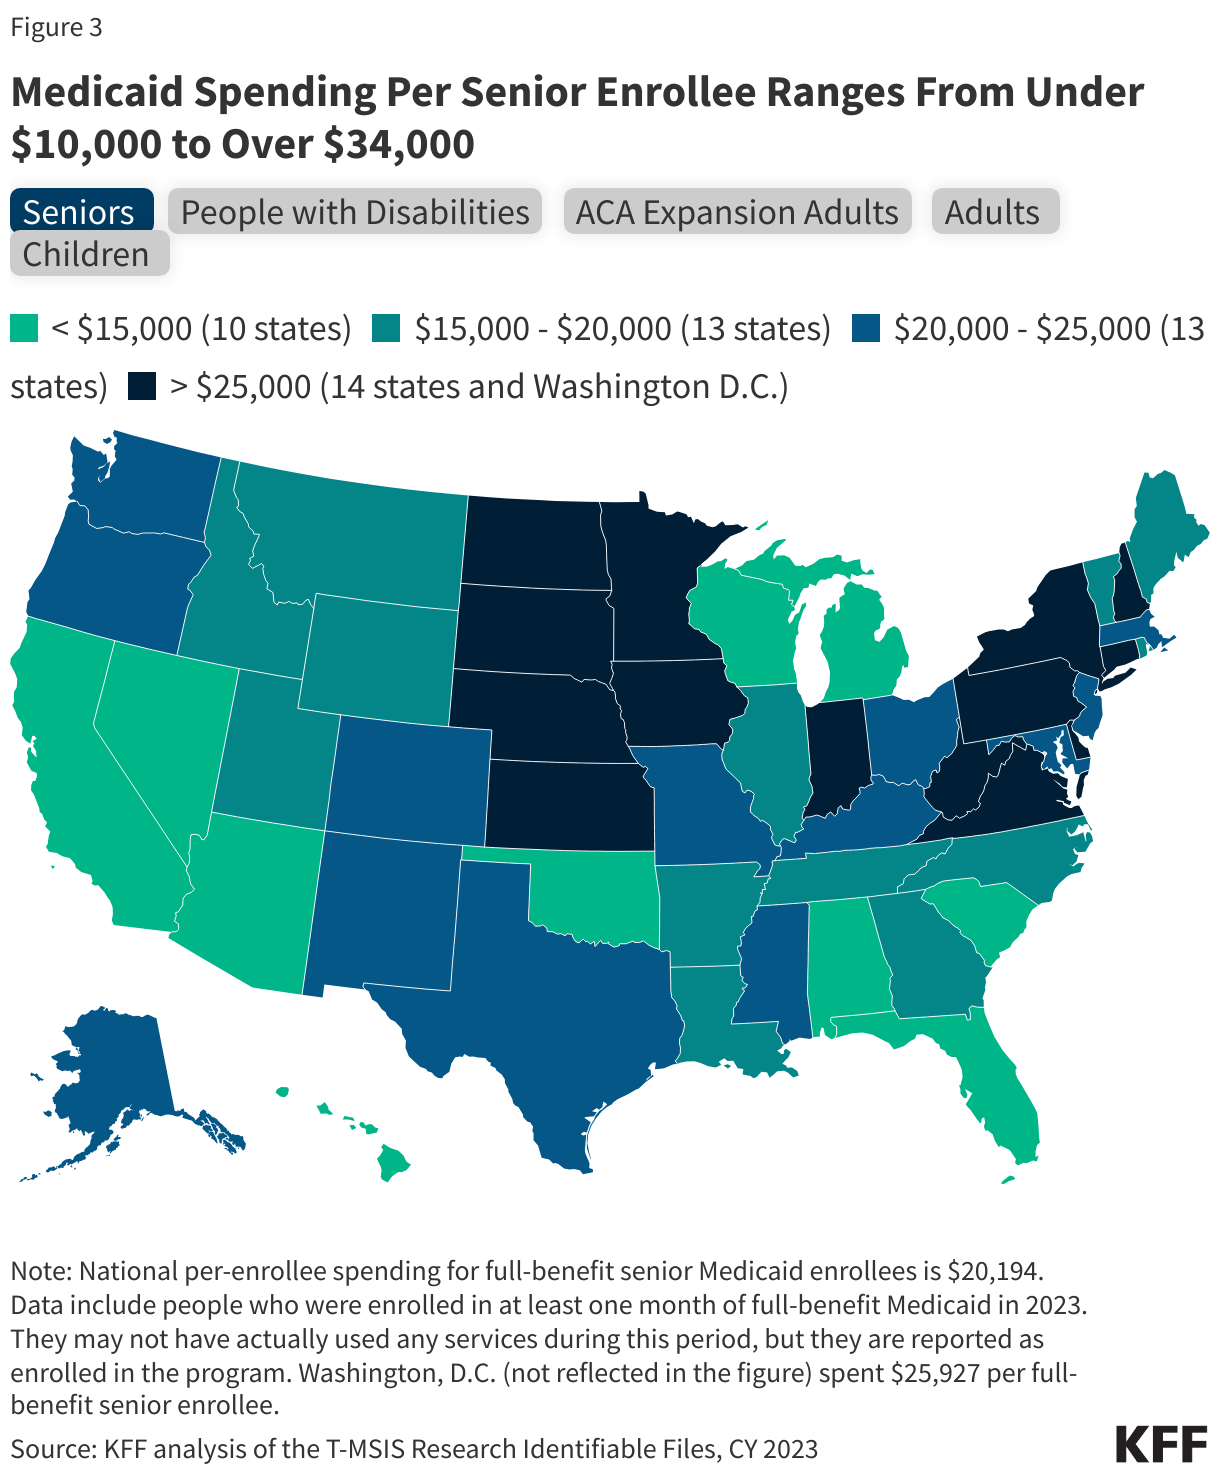
Flexibility for states to determine eligibility levels, benefits, and provider payments in the Medicaid program leads to wide variation in per-enrollee spending across states (Figure 2).

Other factors contributing to variation in per-enrollee spending include variation in state populations and demographics, ability and effort to raise revenue, and variation in health care costs and markets. Across states, Medicaid spending per enrollee ranges from $4,780 to $12,295, with a median spending of $7,909 (Figure 2). Alabama, Florida, Georgia, and Nevada report some of the lowest spending per enrollee, while Washington, D.C., Minnesota, Pennsylvania, and North Dakota report the highest spending per enrollee. Approximately one in seven states have spending greater than $10,000 per enrollee (Figure 2).

Medicaid Spending Per Enrollee Ranges From Under ,000 to Over ,000 (Choropleth map)

Within each eligibility group, there is also considerable variation in spending per enrollee across states (Figure 3).

People with disabilities have the widest variation across states for per-enrollee spending, ranging from $5,040 in Florida to $57,900 in Minnesota (Figure 3). States have considerable flexibility to decide the populations and services covered for long-term care (LTC), which drives large variation in per-enrollee spending for older adults and people with disabilities, who are more likely to use LTC. In contrast, per-enrollee spending for children ranges from $2,227 in Alabama to $5,457 in Alaska (Figure 3). All states must provide comprehensive coverage for children through the Early Periodic Screening Diagnosis and Treatment (EPSDT), which contributes to somewhat less variation in per-enrollee spending for children.

Many—but not all—states that have relatively high or low overall per-enrollee spending tend to see those same patterns across eligibility groups in the state (Figure 3). Some states with the lowest overall per-enrollee spending (e.g. Alabama, Oklahoma) fall among the states with the lowest per-enrollee spending for most eligibility groups (Figure 3). Others, such as Florida and Nevada are more mixed across eligibility groups. For example, Florida, has low per-enrollee spending across all eligibility groups except for children, where it has one of the highest per-enrollee spending. Similarly, some states with the highest overall per-enrollee spending (e.g. Washington, D.C., Delaware) fall among the states with the highest per-enrollee spending for all eligibility groups. However, states like Pennsylvania and Massachusetts are less consistently high across all eligibility groups (Figure 3).

Medicaid Spending Per Senior Enrollee Ranges From Under ,000 to Over ,000 (Choropleth map)

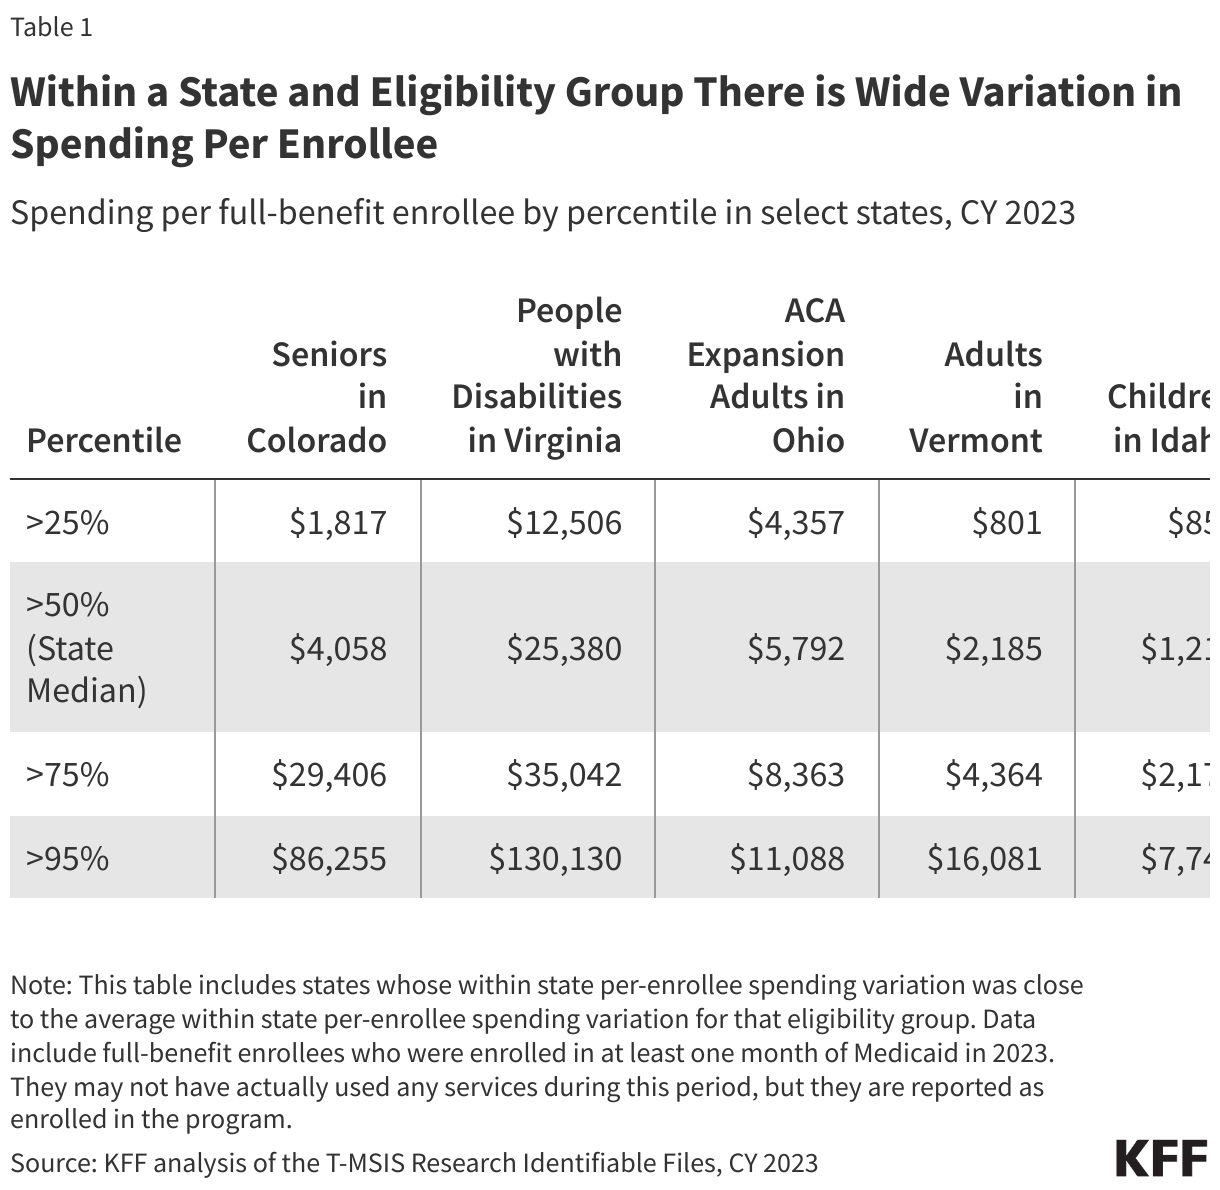
Even within a given state and eligibility group, there is wide variation in spending (Table 1). For example, among people with disabilities in Virginia, 25% have spending less than $12,506 and 5% have spending more than $130,130 – ten times higher (Table 1). Additionally, 25% of seniors in Colorado have spending less than $1,817, and 25% have spending sixteen times greater ($29,406) (Table 1). Despite the generally lower costs for non-disabled adult and child enrollees, the variation in spending for these eligibility groups is wide in Ohio, Vermont, and Idaho as well.

Within a State and Eligibility Group There is Wide Variation in Spending Per Enrollee (Table)

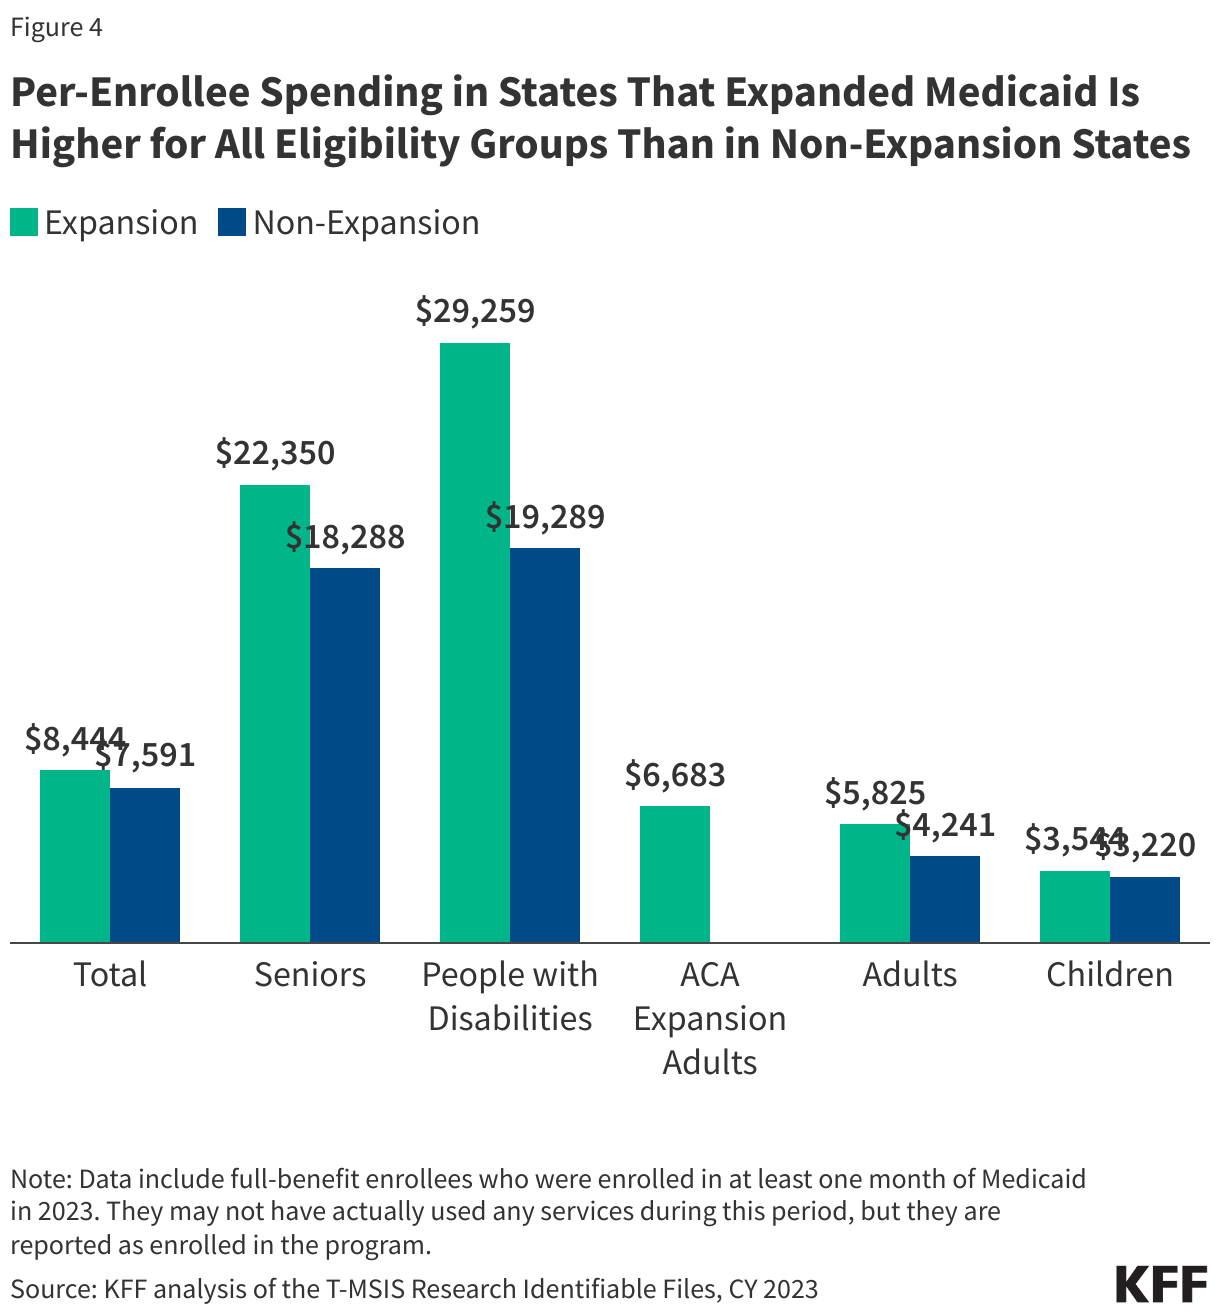
Per-enrollee spending in states that expanded Medicaid is higher for all eligibility groups than in non-expansion states (Figure 4).

Expansion states spend on average $8,444 per enrollee – nearly $1,000 more per enrollee when compared to non-expansion states, which spend $7,591 per enrollee (Figure 4). During debate over the reconciliation bill, some argued that the 90% match rate for expansion adults encourages expansion states to prioritize services for expansion adults of those of other populations—children, parents, people with disabilities, and older adults. However, across all non-expansion eligibility groups, average per-enrollee spending is higher in expansion states than in non-expansion states. For instance, expansion states have an average spending of $29,259 per enrollee eligible based on disability, while non-expansion states spend on average $19,289 per enrollee in the same eligibility group. Similarly, expansion states spend $22,350 per older adult enrollee compared to $18,288 for non-expansion states (Figure 4). These differences in spending may reflect state policy choices about benefits and eligibility, in addition to payment rates, regional variation in health care costs, and state demographics.

Per-Enrollee Spending in States That Expanded Medicaid Is Higher for All Eligibility Groups Than in Non-Expansion States (Grouped column chart)


Methods

Data: The KFF State Health Facts on spending per full-benefit enrollee use the T-MSIS Research Identifiable Demographic-Eligibility and Claims Files (T-MSIS data). This data note is based on State Health Facts data from CY 2023.

Overview of methods: KFF defined full-benefit enrollees as those who are enrolled in Medicaid for at least 1 month with full-benefits or those who received at least one month of benefits through an alternative package of benchmark equivalent coverage. They may have not actually used any services during this period, but they are reported as enrolled in the program and are eligible to receive services. References to dual-eligible enrollees do not include Medicare Savings Program (MSP) enrollees due to the restriction of data to full-benefit enrollees only.

Spending: Spending was calculated by summing the total spending of all claims per full-benefit enrollee in the T-MSIS claims files.

U.S. Public Health

Table of Contents

What is Public Health?

Copy link to What is Public Health?

While there is no singular definition of public health, it has broadly been defined as “the science and art of preventing disease, prolonging life, and promoting health,” and “what we do together as a society to ensure the conditions in which everyone can be healthy”. Definitions and objectives for public health have evolved over time, as it is not a static concept (see Box 1). Public health encompasses a wide variety of programs and activities, including controlling the spread of communicable disease, preventing chronic diseases, improving nutrition, improving air and water quality, promoting safer workplaces, reducing automobile accidents, and more.

The overarching focus for a public health system is to help with disease prevention, health promotion, and to close gaps in health disparities in groups of people. These groups can range from small communities to populations at the national and even global levels. Public health’s focus on health equity in groups of people can be contrasted with clinical medicine, which is mostly focused on preventing and treating illness in individuals.   

Box 1: Selected Definitions of “Public Health”

  • “the science and art of preventing disease, prolonging life, and promoting health through the organized efforts and informed choices of society, organizations, public and private communities, and individuals.” – C-E A. Winslow (1920)
  • “the fulfillment of society’s interest in assuring conditions in which people can be healthy” – Institute of Medicine (1988)
  • “collective effort to identify and address the unacceptable realities that result in preventable and avoidable health outcomes, and it is the composite of efforts and activities carried out by people committed to these ends” – Turnock (2001)
  • “what we do together as a society to ensure the conditions in which everyone can be healthy.” – DeSalvo, et.al (2017)

A Brief History of Public Health in the U.S.

In the United States, public health evolved as a practice and a discipline over time with roots that extend back to the early history of the nation (the first governmental public health agency, the Marine Hospital Service, was formed in 1798). As scientific understanding about causes and effective interventions for diseases improved over time, public health practices evolved and expanded across the country. The 19th century saw a “great sanitary awakening” in the U.S., as illness came to be understood as an indicator of poor social and environmental conditions, and investments in hygiene and sanitation grew to combat disease in communities around the country, especially in large cities. After the U.S. Civil War, states began to set up boards of health to oversee growing investments and attention to public health activities in communities. The first state-level agency for public health was created in New York in 1866; Massachusetts established its first state board of health in 1869 and other states and jurisdictions followed. As the understanding of the germ theory of disease grew, state and local health departments created infectious disease laboratories in the 1890s. In the early to mid-20th century, state and local health departments grew in size and responsibilities and many of the public health interventions and focus areas that we see today were established and expanded.

In addition, a number of milestones occurred in the 20th century to grow the federal government’s role in public health, including new legislation such as the Food and Drug Act of 1906 (allowed federal oversight of manufacture, labeling and sale of foods) and the Sheppard-Towner Act of 1922 (authorized federal government funding of state-level public health efforts for the first time, in this case for maternal and child health programs). As part of the social welfare reforms undertaken via the “New Deal” in the 1930s and the “Great Society” in the 1960s, federal responsibilities, oversight, and funding for public health grew significantly. Many core federal departments and agencies we still have today were established during this period. From the late 1960s through today, U.S. public health efforts have experienced periods of decline and periods of growth often linked with broader social trends, changing perceptions about health threats, and economic and fiscal conditions in the country. During the first Trump administration and continuing through the Biden administration, the COVID-19 pandemic represented one of the greatest public health challenges of the last 100 years and led to an expansion of the government’s public health response. However, the expansion has proven temporary and during the second Trump administration, public health efforts face resource cuts and an uncertain future.

Public health powers and responsibilities derive from the U.S. Constitution and are shared across federal, state, and local levels of government – each of which has unique roles in such efforts that can vary state by state and even community by community. While many of public health efforts are funded and implemented through public (i.e. governmental) programs, private actors are also involved in funding and delivering public health services in the U.S. Given the many actors involved and the variations across federal, state and local roles and approaches, public health in the U.S. has often been referred to as a “patchwork” system.  

Key Public Health Frameworks, Services, Capabilities and Characteristics

Public health efforts are typically guided at the broadest level by strategies or frameworks outlining the services, capabilities and activities that help deliver on the mission to protect and promote communities’ health. A key framework for U.S. public health over the last few decades has been the 10 Essential Public Health Services (EPHS) framework, originally developed in 1994 by a federal workgroup (with input from outside experts), and updated in 2020. The EPHS highlights ten key public health service areas that include: monitoring population health status and community needs, investigating and addressing hazards and health problems, and using legal and regulatory actions to improve and protect the public’s health (see Table 1). An underlying principle of promoting equity underlies all service areas in this framework.

10 Essential Public Health Services (Table)

The “Foundational Public Health Services (FPHS)” framework is another key resource. This framework emerged from a 2013 convening of stakeholders who, in response to a recommendation from the Institute of Medicine, set out to define “a minimum package of public health capabilities and programs that no jurisdiction can be without.” The FPHS, which is now overseen by the Public Health Accreditation Board (PHAB), outlines eight “foundational capabilities” and five “foundational areas” that are central for delivering public health services to communities (see Table 2). These foundational areas include: communicable disease control, environmental public health, and maternal, child & family health, while foundational capabilities include assessment & surveillance, emergency preparedness & response, and communications.

The EPHS and FPHS frameworks overlap but are also seen as complementary, with the EPHS describing activities the public health system overall should undertake in communities, and the FPHS representing a minimum package of governmental public health activities that should be present everywhere.
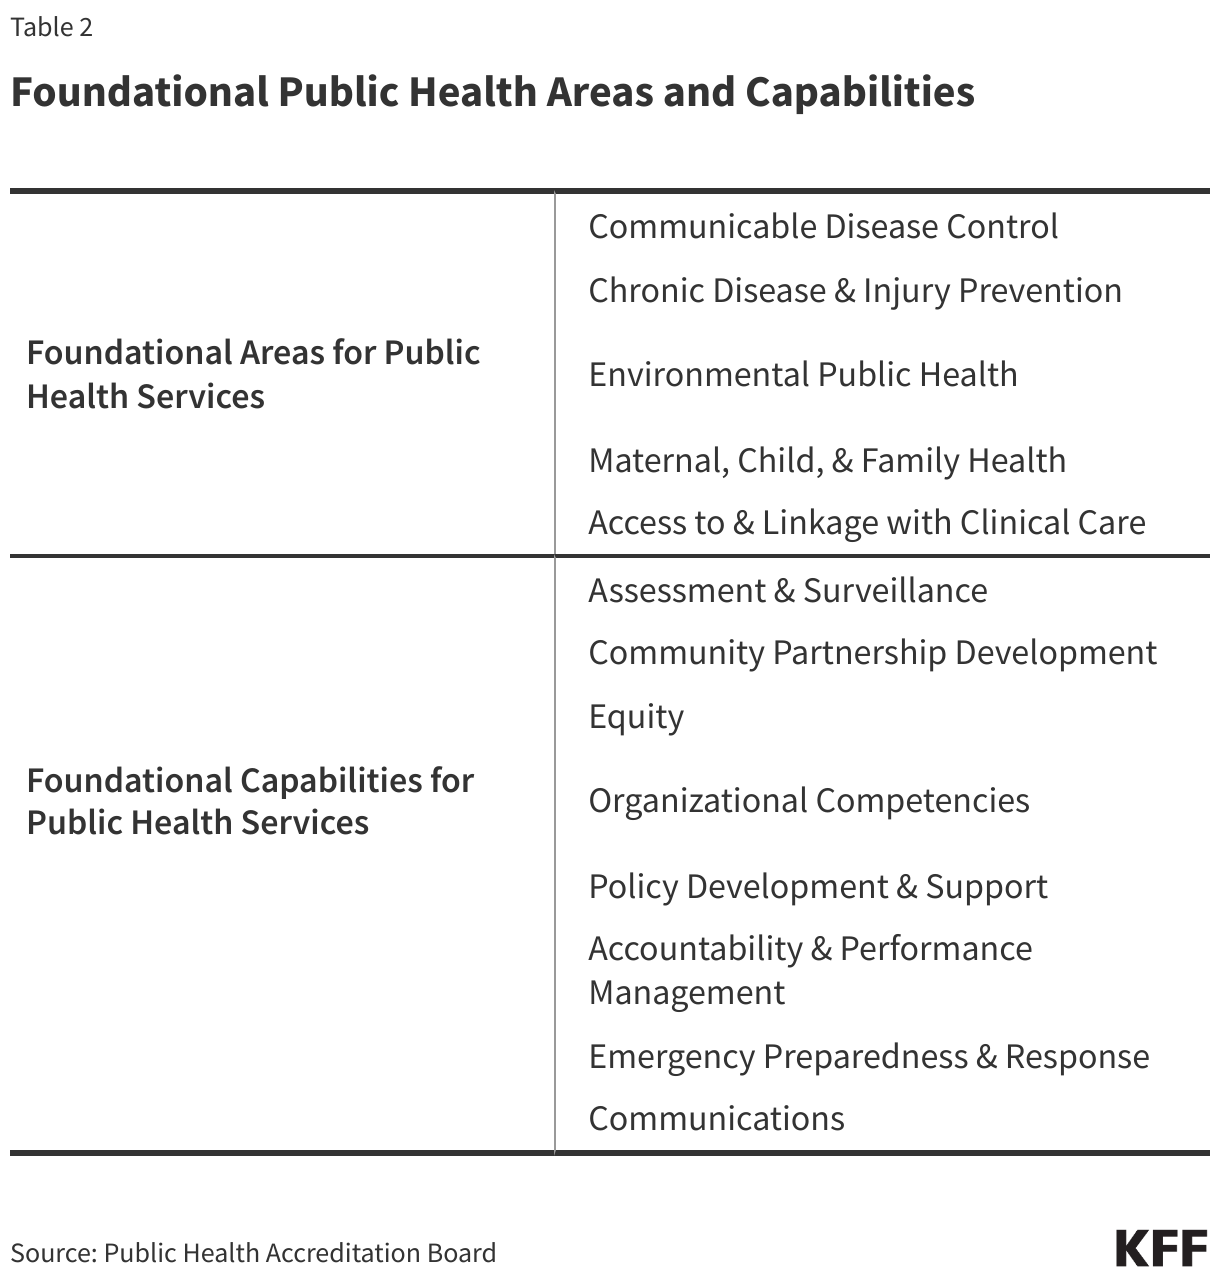
Foundational Public Health Areas and Capabilities (Table)

Other strategies and frameworks have been formed and shaped through numerous governmental and non-governmental expert bodies and reports. Particularly influential have been recommendations and guidance from the National Academy of Medicine (previously the Institute of Medicine), which published a milestone report on the U.S. public health system in 1998 and key follow-up reports in 2002 and 2017.

In addition to these frameworks and capabilities, public health can be identified through certain defining characteristics, which include:

  • Being science-based. Effective public health policies and activities draw from the best available science and evidence and are adapted and updated as new information and scientific understanding improves.
  • Focusing on prevention. Ultimately, the goal of public health interventions is to prevent disease or otherwise improve health outcomes in groups of people. When public health works, the result is often the absence of disease and/or longer, healthier lives in a community. This means the benefits derived from public health interventions – disease prevented – are often unseen and hard to quantify.
  • Addressing health inequities. Underlying the public health approach is a recognition that all people have an equal right to better health. However, in reality there are significant health disparities across different demographic groups and geographic areas. Therefore, public health interventions often emphasize addressing health needs in underserved, marginalized, disadvantaged, and otherwise vulnerable populations in support of health equity.

Social Determinants of Health

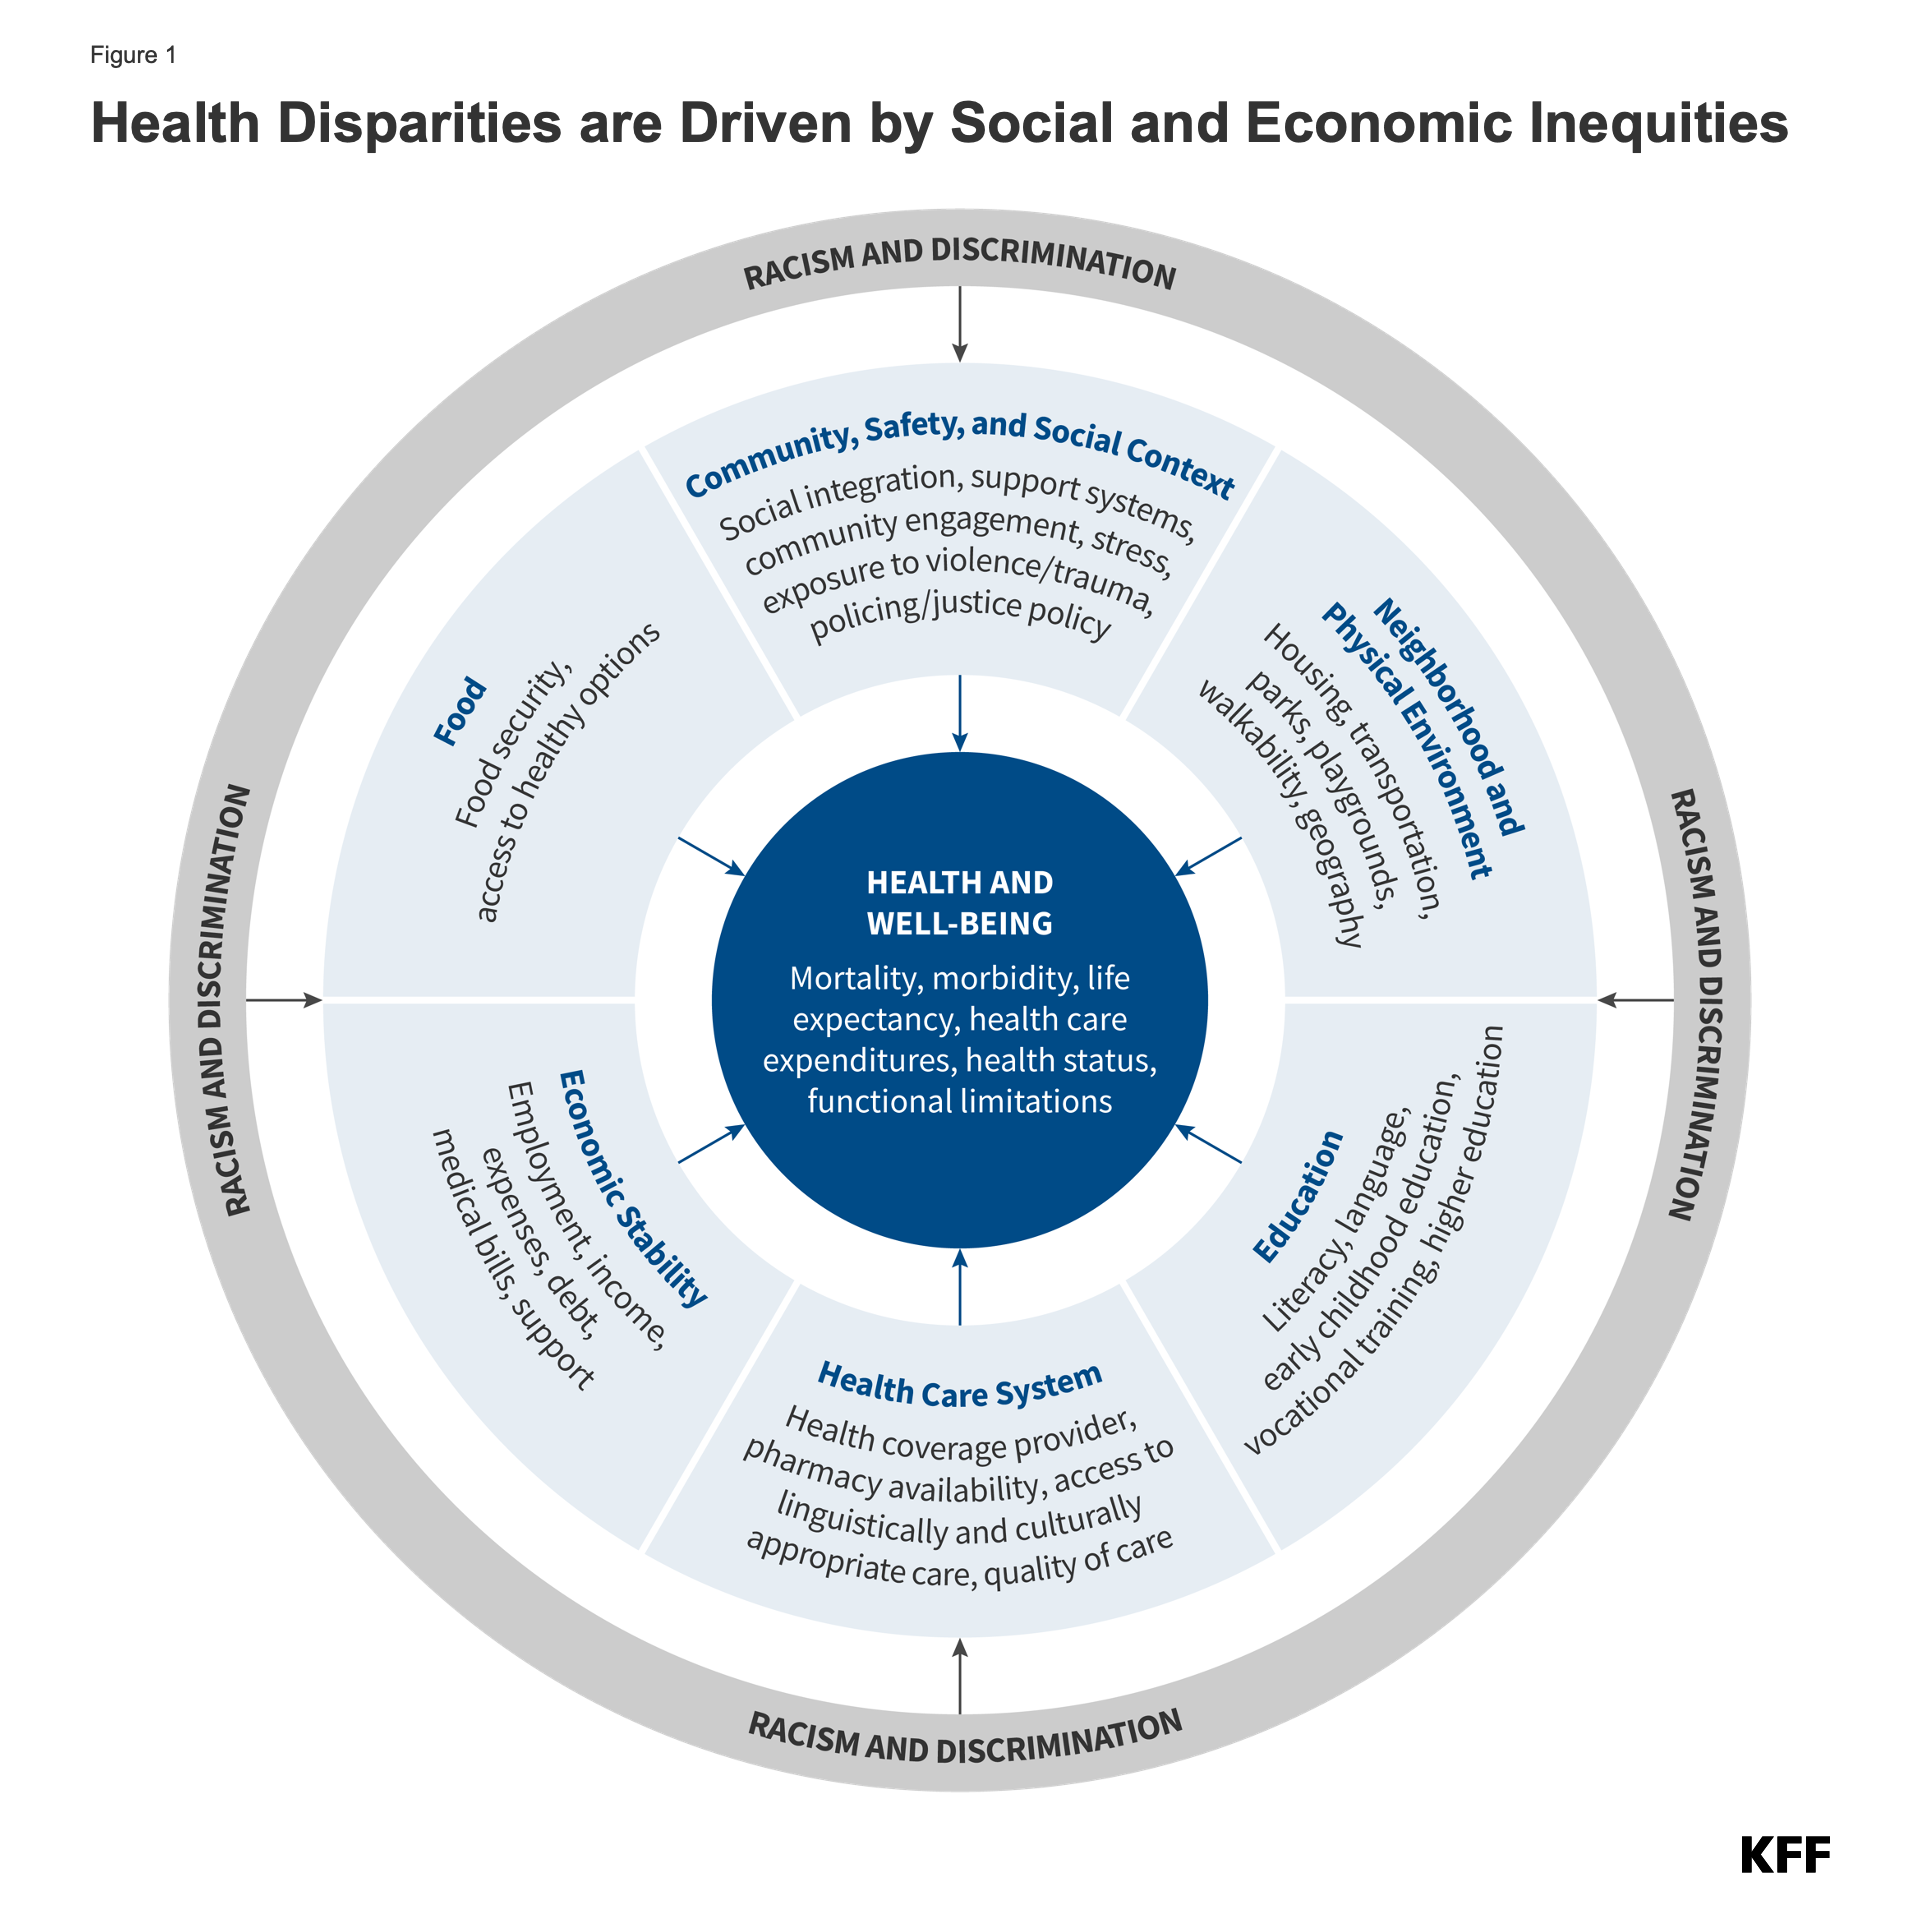
The health of a population can be greatly affected by non-medical factors, which would include things like educational access and quality, health care access and quality, neighborhood characteristics, social and community practices, and economic health and stability. These other, broader societal and community-wide factors are known as the “social determinants of health” (SDOH, see Figure 1). Unequal access to SDOH can feed health disparities. For example, communities that have less access to grocery stores with healthy foods face greater challenges with nutrition, which raises the risks of heart disease, diabetes, obesity and other conditions in these communities compared to others with health food options. During an epidemic or pandemic, the lack of sick leave policies and precarious economic circumstances can leave workers – especially low-wage workers - with little flexibility to take time off from work, raising their risk of infection and continuing community transmission. In general, racial and ethnic health and health care disparities can result in higher rates of illness and death for minority populations across a wide range of health conditions.

Many public health programs recognize the importance of social determinants of health, and sometimes work in partnership with other public and private efforts to help develop and implement complementary approaches aimed at improving health equity. The CDC recommends that public health departments consider how social determinants affect health in their communities, highlighting how a focus on implementing the 10 Essential Public Health Services can help address inequities that arise from these social conditions. Still, there are limits to how directly public health programs can address these issues given that they often involve broad social conditions such as employment, discrimination, housing, and education.

Source: KFF. Race, Inequality, and Health. https://www.kff.org/health-policy-101-race-inequality-and-health/?entry=table-of-contents-what-factors-drive-racial-and-ethnic-health-disparities
How Is Public Health Governed and Delivered in the U.S.?

Copy link to How Is Public Health Governed and Delivered in the U.S.?

As indicated in the name, “public” health is primarily shaped and supported through the public sector, i.e., governments. In the U.S., public health powers and responsibilities are shared across federal, state, and local levels of government. Legal authorities for public health powers are derived from the U.S. Constitution and relevant federal, state, and local laws (see Box 2 for an overview of the legal basis for U.S. public health powers). A set of public health departments and agencies at each of these levels forms the organizational backbone of the U.S. public health system. However, many private sector actors, such as non-governmental community-based organizations, academic institutions, private companies, philanthropies, and others, also have roles in the public health system.


Box 2: Legal Basis for State and Federal Public Health Powers

The U.S. Constitution does not mention public health specifically, but certain powers granted to the federal government and to states in the Constitution have been interpreted as encompassing public health. For example, under the 10th Amendment’s “police powers” clause, states are granted primary responsibility for enacting and enforcing laws to promote the health, safety, and general welfare of people in their jurisdictions, which is understood to include public health. This means that in the U.S., state governments often have primary responsibility for enacting public health measures and deciding on public health policies. During public health emergencies, states also have primary authority to impose and rescind certain measures within their jurisdiction such as business restrictions and school closings.

The Constitution also grants some powers to the federal government. Under the Constitution’s “commerce clause,” the federal government has exclusive authority to regulate interstate and foreign commerce. For public health, this means the federal government has authority to impose quarantines or other health measures that concern the spread of diseases into the U.S. from foreign countries and/or across state lines. The federal government’s Constitutionally derived power to tax and spend for the general welfare provides it the ability to use federal resources in support of public health activities in states and localities nationwide.

Even so, the lines between where federal and state public health powers begin and end – and how these powers are balanced with other legal concerns – are not always perfectly clear and can shift over time. Sometimes, existing rules or practices are challenged in court or changed through new legislation. For example, the Supreme Court in its Jacobson v Massachusetts decision in 1905 established that states can enforce compulsory vaccination laws, setting a precedent that public health concerns can sometimes outweigh individual rights. This and subsequent rulings upholding this principle have been a legal cornerstone for state-level vaccination requirements, such as those for school-aged children. However, in recent years many state legislatures have passed laws intended to weaken vaccination requirements or eliminate them entirely. In addition, during the response to COVID-19, many government-imposed public health interventions such as mandatory masking, social distancing, and vaccination requirements were challenged through legal action.

Federal Government

Each of the three branches of the federal government (Executive, Legislative, and Judicial) has a role in shaping and implementing public health in the U.S.

The President (Executive Branch)

Federal responsibilities and oversight of public health are spread across numerous executive branch agencies and departments overseen by the President (also see “Congress and the Executive Branch and Health Policy). The President, White House, and executive branch agencies also have the authority to set certain aspects of national public health policy, such as determining under which circumstances and for what diseases that individuals entering the U.S. may be subject to quarantine, isolation, and/or other public health measures, invoking border and migration control measures for public health issues such as those allowed under Title 42, and instituting public health controls or other measures on interstate travel and commerce.

The key federal departments and agencies involved in oversight and implementation of public health in the U.S. include:

Department of Health and Human Services (HHS) currently has 13 operating divisions and is overseen by[RS1]  a secretary, with multiple assistant secretaries responsible for specific offices and programs. For example, the Office of the Assistant Secretary of Health (OASH) oversees key HHS public health offices and regional offices, as well as the U.S. Public Health Service Commissioned Corps. Also within OASH is the Office of the Surgeon General, which has historically served as a center for expertise on many public health issues and has at times released influential reports, affecting U.S. public health policy and practice in areas such as tobacco, HIV/AIDS, and drunk driving. A reorganization of the department has been proposed, which, if enacted, would reduce the number of operating divisions and shift the organizational locations of some offices at HHS (more below). The following are the core public health-focused operating divisions within HHS:

  • Centers for Disease Control and Prevention (CDC) is considered the leading public health agency of the federal government. The CDC is comprised of a central Office of the Director, nine national centers covering different areas of U.S. public health, and a center for global health. CDC houses experts, laboratories, communication services, and other capabilities directed to improve the public’s health and respond to emergencies. One of CDC's core functions is to support state and local public health efforts through funding and technical assistance. CDC’s budget includes an annually appropriated discretionary amount provided by Congress each year (CDC’s FY2024 enacted budget for its core public health programs was $9.25 billion), and also several programs whose budget is determined by specific Congressionally-mandated program authorizations, such as the Vaccines for Children program (in FY2024 the budget for these mandatory programs totaled $8.03 billion). During outbreaks and other health emergencies, Congress has often provided additional emergency supplemental funding to support CDC response activities. CDC is led by a director, historically appointed by the President without need for Senate confirmation. Due to a law passed by Congress in December 2022, the CDC director position is a Senate-confirmed position as of January 2025.
  • Food and Drug Administration (FDA) is responsible for protecting public health by ensuring the safety, efficacy, and security of human and veterinary drugs, biological products, and medical devices. FDA also works to maintain the safety of (some of) the U.S. food supply, cosmetics, and products that emit radiation. FDA review and authorization/approval is necessary for all prescription drugs and all vaccines intended for use in humans, along with many other medical products and health devices. The total program level budget at FDA (the amount of money the FDA can spend for its activities) is comprised of both Congressionally appropriated funds and user fees collected via regulatory review of many of the products under FDA’s purview. In FY2024, the FDA’s total program level budget was $7.2 billion, of which $3.3 billion (46%) came from user fees. The FDA is led by a commissioner, a Senate-confirmed position.
  • Administration for Strategic Preparedness and Response (ASPR) is an operating division within HHS that leads medical and public health preparedness for, response to, and recovery from disasters and other public health emergencies. This includes activities to support development of medical countermeasures for health emergencies, a stockpile of emergency medical supplies and equipment for use during emergency responses, and support and technical assistance to state and local public health agencies to improve their response capacities. It is comprised of multiple centers, including the Center for Preparedness, the Center for Response, the Center for the Biomedical Advance Research and Development Authority (BARDA), and the Center for the Strategic National Stockpile. ASPR’s operating budget for FY2024 was $3.65 billion. ASPR is led by an Assistant Secretary for Preparedness and Response, a Senate-confirmed position.
  • Other HHS Operating Divisions: Other HHS agency programs also play a role in public health, including by helping to build capacity, respond to outbreaks and serve communities, even if they may be more directly focused on clinical care and services, including HRSA’s community health center program and Ryan White HIV/AIDS Program, and SAMSHA’s programs on substance abuse and mental health.

The current Trump administration announced there will be a reorganization of these HHS operating divisions.  For example, the administration proposed to create a new agency called the Administration for a Healthy America (AHA) that would consolidate several existing HHS agencies, including OASH, HRSA, SAMHSA, and expects to place ASPR within CDC, among other changes.  

Several other departments and agencies outside of HHS play a role in promoting the nation’s public health.

These include:

  • U.S. Department of Agriculture (USDA), which supports U.S. agriculture through assistance to farmers, and also oversees programs aimed at improving health, ending hunger, ensuring food safety, and other areas. USDA also protects public health through regulating aspects of the nation’s food supply and also providing food services for children and low-income people across the country. USDA’s Food Safety and Inspection Service (FSIS) regulates processors of meat, poultry, and eggs, and helps respond to foodborne disease outbreaks. The department’s Food and Nutrition Service oversees programs to provide food and nutrition education in schools as well as the Supplemental Nutrition Assistance Program (SNAP), which provides food benefits to low-income families.
  • Department of Defense (DoD) oversees programs focused on the health and safety of active-duty military members and their families, and also supports a number of public health functions such as health surveillance and emergency response.
  • Department of Homeland Security (DHS) provides support to help state and local public health agencies improve preparedness and response to terrorism and other public health threats.
  • Occupational Safety and Health Administration (OSHA) in the U.S. Department of Labor works to promote safe and healthy working conditions nationwide through setting and enforcing standards, and implementing training, outreach, education, and other assistance programs for worker safety.

Department of Veterans Affairs (VA) oversees programs focused on the health of military veterans and their families, including public health programs to help promote health and prevent disease in these populations.

This is not meant to be a comprehensive list; other federal agencies also have responsibilities and activities important for public health.

U.S. Congress (Legislative Branch)

Congress (the House of Representatives and the Senate) makes laws, conducts oversight of the Executive branch, and determines the level of federal spending; all roles that are relevant to the U.S. public health system. Much of the federal funding for public health is for discretionary programs rather than mandatory ones (see Funding below), so Congress must come to agreement and pass bills annually to determine how much money goes to these programs. Congress may pass additional emergency funding to states and localities for public health efforts during national emergencies, such as was done numerous times during COVID-19. Congress may also pass laws that change federal practices related to public health, such as a 2022 law that made the CDC director a Senate-confirmed position. Oversight responsibilities for public health in the legislative branch are divided across a number of different Congressional committees with jurisdiction over different aspects of public health policy, and oversight of different Executive branch agencies and departments working in public health.

Federal Courts (Judicial Branch)

U.S. federal courts, up to and including the Supreme Court, pass judgment on how or whether federal public health laws and policies can be carried out and settle disputes between the federal government, individuals, states, and private companies over how public health activities are regulated and implemented. The legal basis for many current public health practices, such as vaccination requirements, rests on federal court decisions and precedents (see Box 2). Federal courts have also weighed in on the legality of a number of federal public health policies enacted during the response to COVID-19, such the CDC masking requirement for public transportation issued in January 2021 that was challenged and ultimately overturned by a federal court in April 2022, and the COVID-19 vaccination mandate for federal workers implemented by the Biden administration in September 2021 that was ultimately rescinded after legal challenges were raised in federal courts.

State, Local, and Territorial Governments

States are given primary responsibility for many public health powers under the U.S. Constitution (see Box 1). Each of the 50 states plus Washington D.C., five U.S. territories (American Samoa, Mariana Islands, Guam, Puerto Rico, and the Virgin Islands), and three associated states (Marshall Islands, Micronesia, and Palau) has public health departments that are responsible for implementing public health programs in their jurisdictions. Funding for public health programs at the state and local levels comes from a combination of federal, state, and other sources (see funding section below).

Across States, Public Health Governance Varies

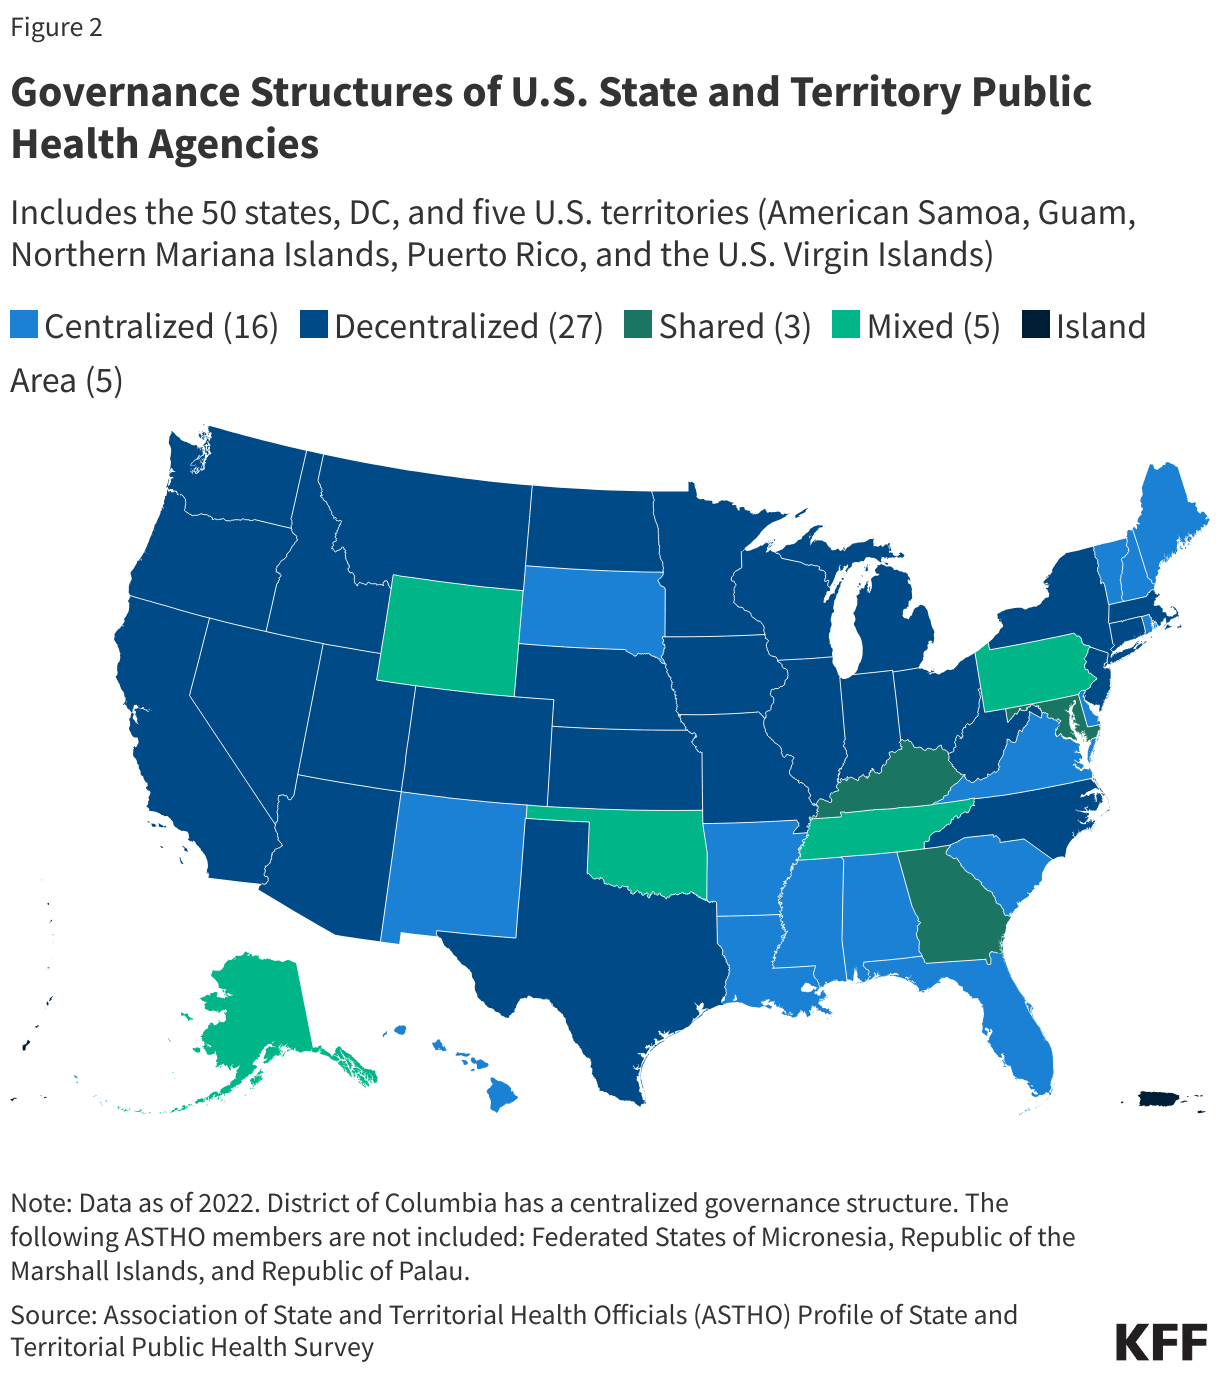
How public health is governed differs across these states and territories. Some have a very centralized governance model, where most or all parts of the state are served by local units of the state health agency and primary decision-making powers reside with state representatives. Others have a more decentralized governance structure, where most or all parts of the state are served by local public health agencies that may be independent of the state health agency. Still others have a mixed or shared approach to public health governance between the state and local decision makers. A 2022 analysis by the Association of State and Territorial Health Organizations (ASTHO) found that of the 50 states and D.C., 16 are centralized, 27 decentralized, and 8 have a mixed or shared approach to governance (See Figure 2).

U.S. map showing governance structures of state and territorial public health agencies in 2022. Decentralized governance is the most common model, used by 27 states, while 16 states and Washington, D.C., have centralized systems. Three states have shared governance structures, five have mixed structures, and the five U.S. territories shown are categorized as island areas. The map highlights substantial variation in public health governance across states and territories.

This variation in governance leads to very different processes across states for how public health policy is determined and implemented. While more decentralized public health governance can result in public health programs that are more tailored to the needs of specific areas, it can also make coordinated public health action more challenging, especially during outbreaks and pandemics, as occurred during COVID-19.

Common Public Health Activities at the State Level

According to a 2022 survey conducted by ASTHO, the activities most commonly implemented by state public health agencies in 2022 included:

  • communicable disease screening, prevention, and treatment, such as for HIV/AIDS and sexually transmitted diseases (all 51 state health agencies, including D.C., provide these services);
  • public health surveillance such as tracking chronic and communicable diseases as well as injuries (all 51 state health agencies);
  • immunization support, including managing orders and distributing vaccines for children and maintaining a childhood immunization registry (all 51 state health agencies);
  • laboratory services such as foodborne illness testing and influenza virus typing (50 state health agencies, all except Kentucky).

Other very common public health activities across states include: chronic disease prevention, family planning, maternal and child health home visits, tobacco cessation and prevention programs, food safety, inspection and training programs, and cancer screenings.

Local and Tribal Health Agencies

Even as state governments have the primary mandate to oversee public health policies and programs, many public health programs within states and territories are implemented through local (such as regional, county, city, and tribal) health departments. According to the National Association of County and City Health Officials (NACCHO), over 3,300 local health agencies are responsible for implementing public health programs across the country. Depending on the governance model present in each state, these local public health departments may have more or less autonomy regarding public health in their jurisdictions. Some areas may have local boards of health authorized by state laws, which establish guidelines for the operation of public health programs at more local level jurisdictions. In addition, under U.S. law, the 574 federally recognized American Indian and Alaska Native tribes and villages have many powers of self-government, which include responsibilities for implementing public health programs. Given this varied approach across states and at the local level, the U.S. is often referred to as having a “patchwork” public health system.

Non-governmental/Community-Based Actors

Also important for public health are a wide variety of non-governmental, including community-based, actors. This includes the public health professional associations that often advocate for and represent public health practitioners, such as the aforementioned ASTHO and NACCHO, plus the Council of State and Territorial Epidemiologists (CSTE), the Association of Immunization Managers (AIM), the American Public Health Association (APHA), Trust for Americas Health (TFAH), community-based organizations, philanthropic organizations, and many others. Colleges and universities are also important: there are at least 66 schools of public health, 164 public health programs, and 29 baccalaureate public health programs at institutions of higher learning in the U.S., which support research, training, and education programs in this field. A host of private companies are important for U.S. public health functions, including pharmaceutical and medical device companies, laboratories, and many others.

Public Health Funding

Copy link to Public Health Funding

Funding for public health comes primarily from government spending, which includes federal funding (both regular and supplemental appropriations) passed through to state and local governments via grants and cooperative agreements, as well as funding appropriated by state governments, and funds from city, county, district, and other local governmental sources. In addition, there may be non-governmental sources of funding for public health services, such as those from philanthropic and other private organizations. Over the last twenty years there have been periods of funding declines and growth for public health in the United States – sometimes referred to as a “boom-bust cycle” of support. For example, between 2010 and 2019, spending for state public health departments declined by 16% and spending for local public health departments declined by 18%, by some estimates. However, during the COVID-19 pandemic, public health budgets grew due to an influx of federal, state, and other response funding.

Estimating how much funding is directed to public health across the U.S. is challenging for a number of reasons. For one, there is variation across federal agencies & departments, states, and local governments on how “public health” spending is defined and how that data is collected, resulting in a lack of standardization and comparability. Second, public health programs may draw from and blend multiple sources of funding across federal, state, and local sources, making tracking and de-duplicating funding estimates challenging. Also, many public health departments, particularly at the state and local levels, have limited capacity and lack the resources and systems necessary to effectively track and report spending. Recognizing these challenges, there are sources we can look at that provide some idea about how much is spent on public health at the federal, state, and local levels:

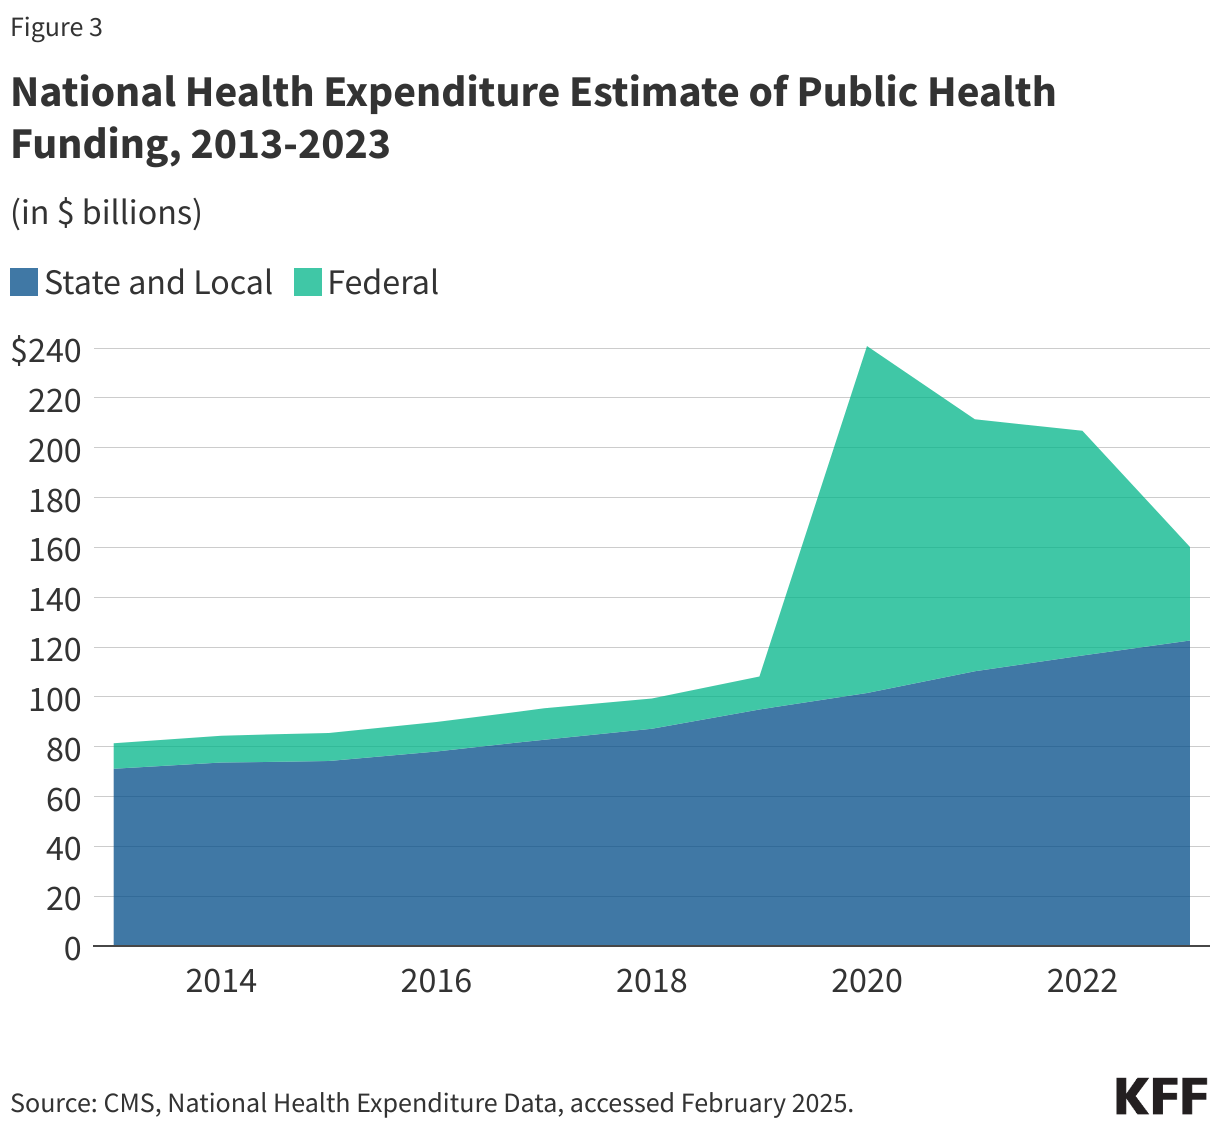
  • National public health spending estimates. One commonly cited estimate for national-level public health spending is the Centers for Medicare and Medicaid Services (CMS) Office of the Actuary’s National Health Expenditure Accounts (NHEA) data, which includes an annual Public Health Activity Estimate (PHE) for federal, and state and local spending on public health (as well as an estimate for all health spending). Figure 3 shows the PHE for federal, state and local public health spending between 2013-2023, ranging from a low of $80 billion in 2013 to a high of over $240 billion in 2020. Until 2020, these data indicated that the bulk of public health funding in the U.S. came from state and local sources. This changed during COVID-19, due to a massive increase in federal public health funding in 2020-2022 through supplemental (emergency) appropriations; the latest available data (from 2023) indicate that 3.3% of all U.S. health spending was directed to public health ($160 billion out of $4.87 trillion in total health spending). Some researchers who have studied the PHE believe it to be an overestimate of actual spending on public health.
Stacked area chart showing national public health spending from federal and state/local sources from 2013 to 2024. Total public health funding rose gradually from about  billion in 2013 to about 0 billion in 2019, surged to more than 0 billion in 2020 due to a sharp increase in federal spending, then declined but remained above pre-pandemic levels through 2024. State and local funding increased steadily throughout the period, while federal funding accounted for most of the pandemic-era spike and subsequent decline.
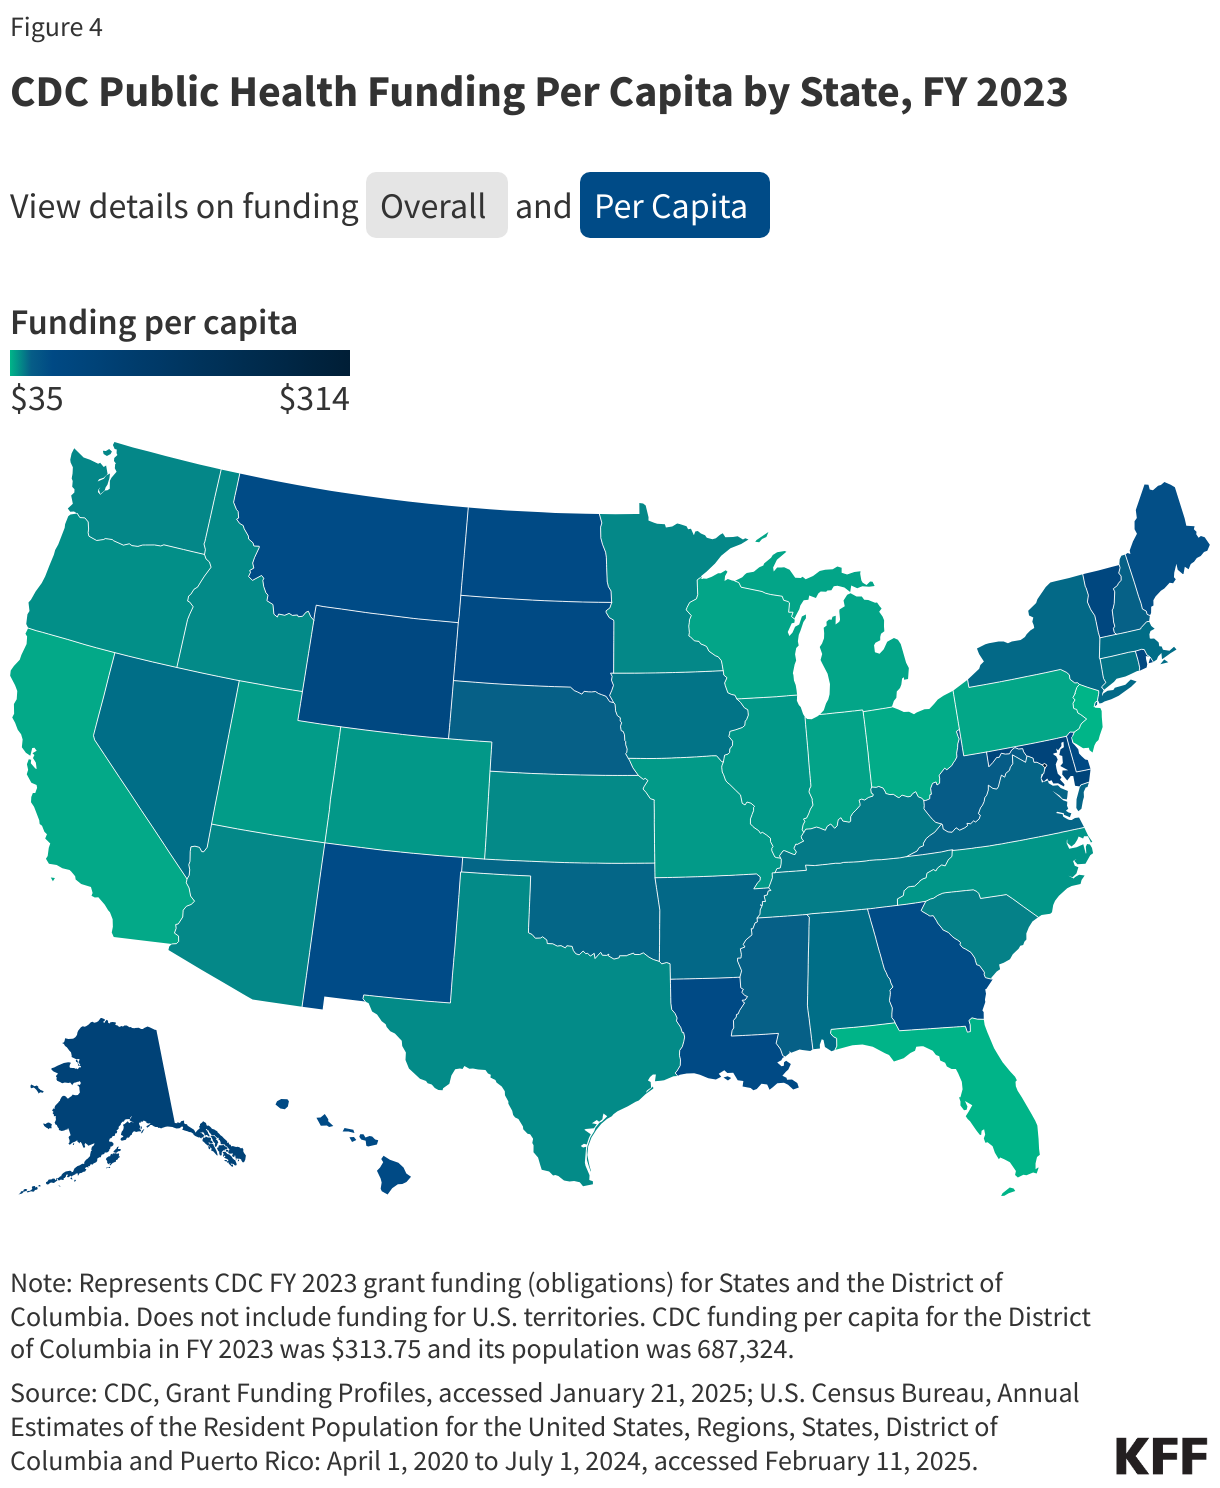
  • Individual departments and agencies. Some departments and agencies release data on how much funding they provide to public health programs nationally, which represent a subset of national public health spending amounts. For example, CDC provides annual spending data on all its grants, cooperative agreements, and emergency appropriations directed to state and local public health departments (CDC public health funding profiles). The CDC reported that it provided over $15 billion in grants to health departments across the country in FY2023, which includes funding derived from CDC’s core discretionary funds as well as mandatory funds for programs such as Vaccines for Children. The top state recipients (per capita) of CDC funds included Washington, D.C., Alaska, Maryland, and Vermont (see Figure 4).
Choropleth map showing CDC public health grant funding per capita by state in fiscal year 2023, ranging from  to 4 per resident. Per-capita funding varies widely across states, with generally higher levels in Alaska and several Mountain West, New England and Mid-Atlantic states, and lower levels in parts of the South and Midwest. The map highlights substantial geographic differences in CDC public health funding on a per-person basis.
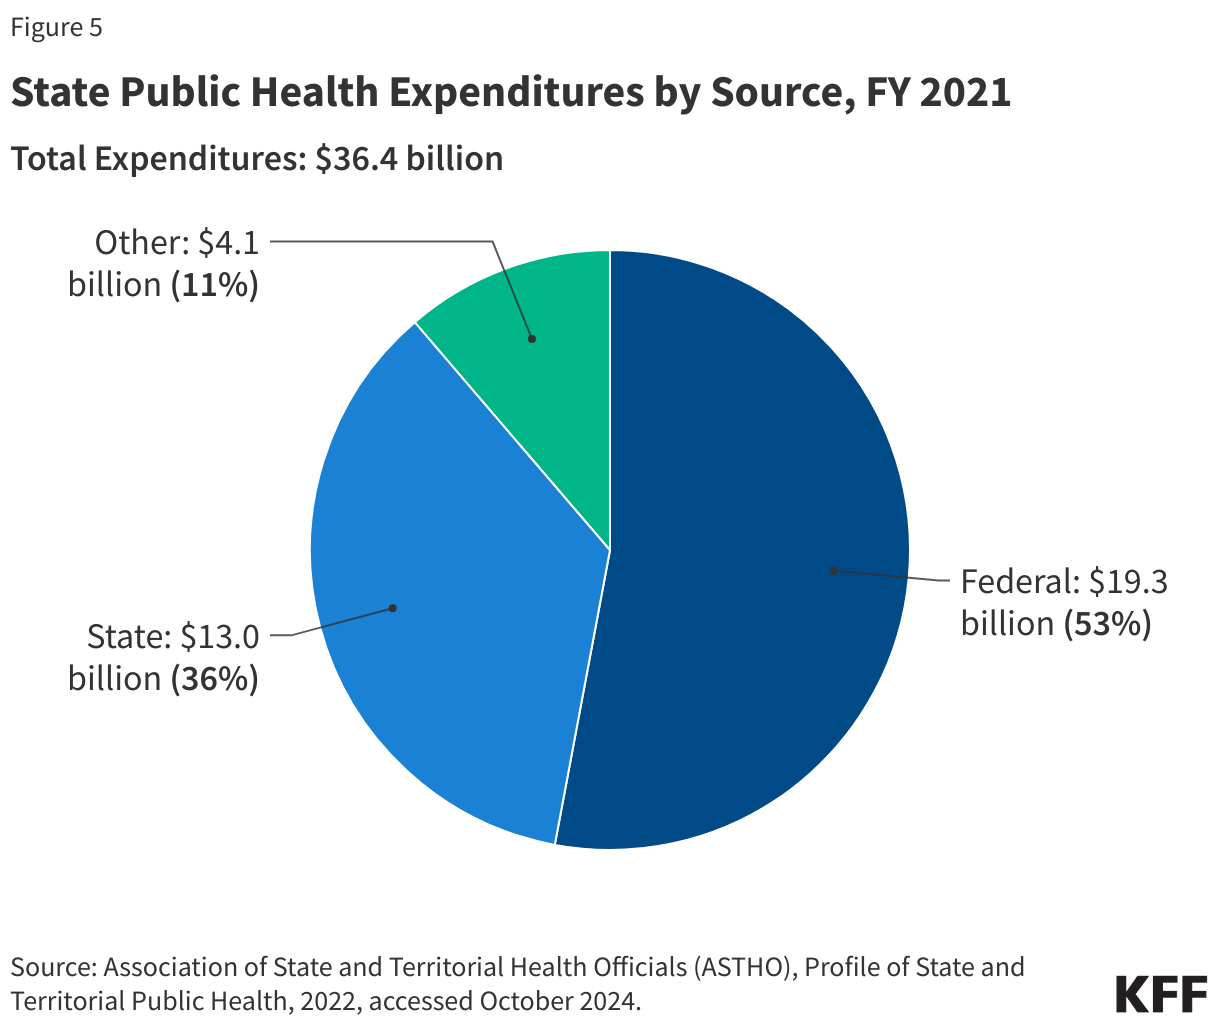
  • State-level public health funding estimates. State spending on public health budgets comes from a combination of federal, state, and other sources. According to the ASTHO, in FY2021 (the latest data available, which came during the COVID-19 pandemic response that featured significant federal supplemental appropriations), federal sources comprised the largest share of state health department budgets (53%), followed by state sources (36%) and other sources (11%, see Figure 5).
Pie chart showing sources of state public health expenditures in fiscal year 2021, totaling .4 billion. Federal funding was the largest source at .3 billion, or 53% of expenditures, followed by state funding at .0 billion, or 36%. Other sources accounted for .1 billion, or 11%. Federal funds provided the majority of state public health spending.

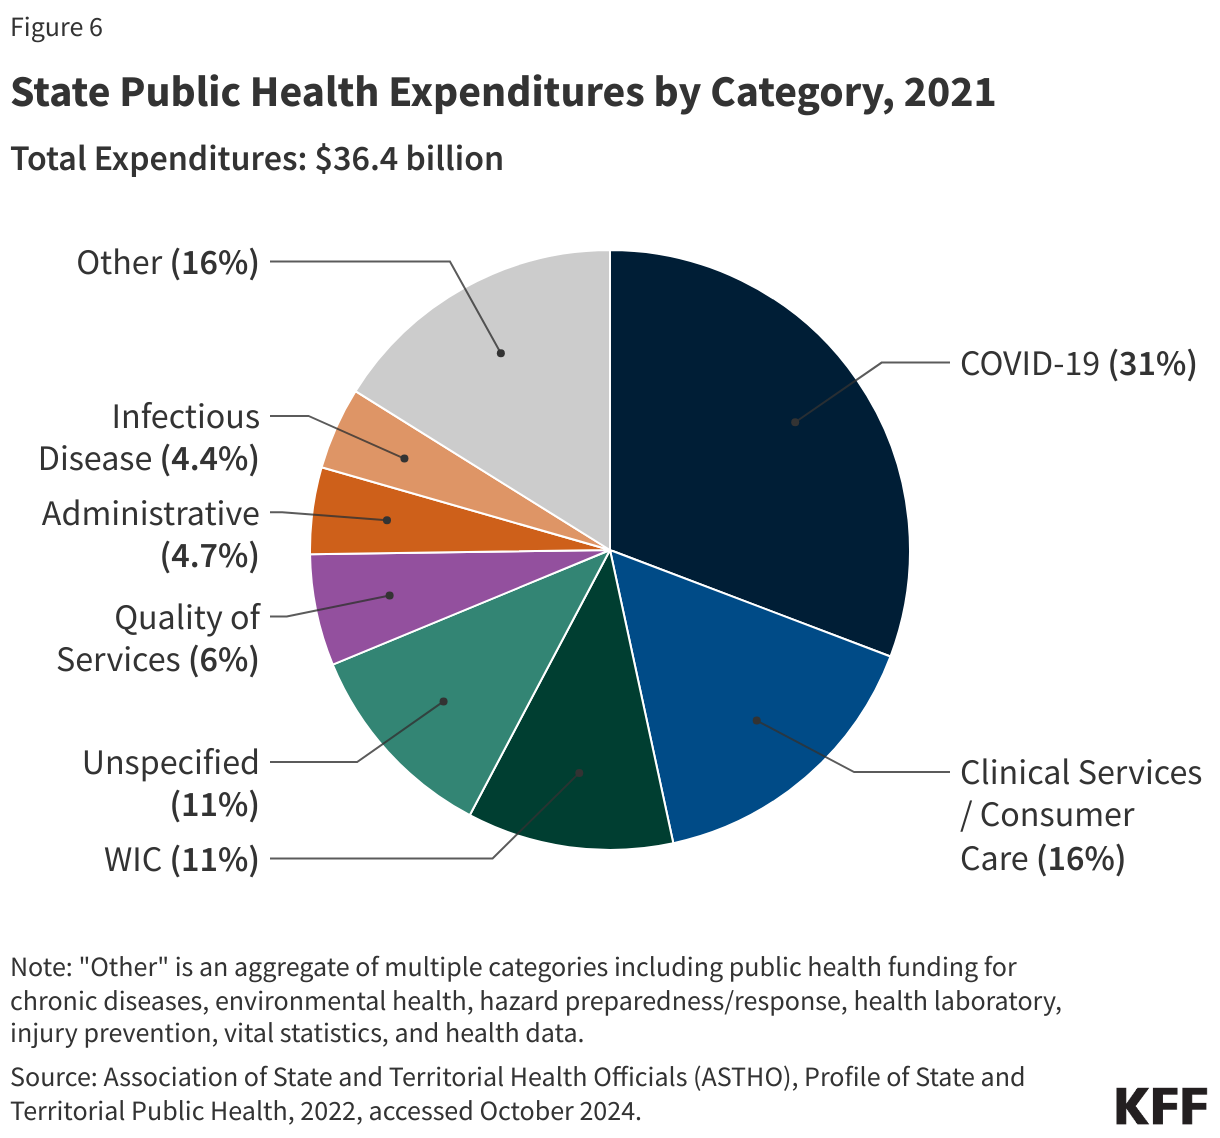
ASTHO also reports that the largest category of state public health expenditure in 2021 was COVID-19 response activities, followed by clinical care services, and women, infants, and children (WIC) programs (see Figure 6). ASTHO data from 2018 (the most recent pre-pandemic year with data available) show the largest categories of public health expenditure then were clinical services (30%) and Women, Infants and Children (WIC) programs (23%).

Pie chart showing state public health expenditures by program category in 2021, totaling .4 billion. COVID-19 accounted for the largest share of spending at 31%, followed by clinical services and consumer care at 16%. Other spending categories included an aggregate “other” category at 16%, WIC at 11%, unspecified programs at 11%, quality of services at 6%, administrative functions at 4.7%, and infectious disease programs at 4.4%. COVID-19 response represented the largest single area of state public health spending in 2021.
  • Public health spending at the local (city/county/tribal) level: NACCHO reports that in 2021, local health departments drew a majority of their budgets from federal sources (55%, which included pass-throughs (26%), direct funding (25%), and Medicaid/Medicare-related sources (4%)). A further 21% came from state sources, 14% from local sources, and the remaining 10% from other sources. In 2021, NACCHO reports the mean and median annual expenditure per capita on public health by local health departments were $78 and $49, respectively.
  • Funding gap estimates: One study suggests that foundational public health capacities require an overall investment of at least $32 per person per year from all levels of government but, as of 2019 (prior to the COVID-19 pandemic), investment in public health capabilities was approximately $19 per person, indicating at least a $13 gap in annual per-capita spending on public health. While funding increased significantly during the COVID-19 pandemic, much of that support is time-limited.

Public Health Workforce

Copy link to Public Health Workforce

The public health workforce includes persons working for federal, state, and local health departments as well as those in the private sector working in community-based and voluntary organizations, hospitals and health care systems, and schools. Responsibilities for these workers can include providing health care services in public clinics, collecting and analyzing data; performing health inspections and safety monitoring at places of work, residence, and recreational facilities; developing, administering, and evaluating public health programs and policies; and providing public health education and communication services to communities, among others.

Over the last twenty years local public health departments have faced a general decline in workforce numbers in line with declines in public health budgets, with the notable exception of a rise in workforce funding due to additional federal funding (and more state and local funding) in response to the COVID-19 pandemic, although this support was time-limited. One study estimates between 2009 and 2019, the number of workers at local health departments dropped from 162,000 to 136,000, a 17% decline that translates into a loss of more than 1 worker per 10,000 residents served. Subsequently, additional funding from pandemic response led to growth in the public health workforce, even if temporarily: NACCHO estimates that in 2022 there were 182,000 public health workers at local health departments nationwide, the highest total in at least two decades. Looking specifically at the epidemiologist workforce, the Council of State and Territorial Epidemiologists (CSTE) estimates 5,706 epidemiologists worked at health departments of the 50 states and DC in 2024, which is a 38% increase over the 4,135 reported in 2021. These national numbers, however, mask an uneven distribution of the public health workforce, as rural health departments have low per-capita staffing numbers compared to large, primarily urban health departments.

Workforce retention has been an issue before, during, and after COVID-19, and is exacerbated now as pandemic-era funding expires. NACHHO and CSTE point to impending workforce losses and note that, despite the recent growth in the workforce, there is still a large gap between current staffing levels at health departments and what is needed to fully implement Foundational Public Health Services nationwide. In addition, the public health workforce faces stress, burnout, and relatively low pay, which contributes to turnover and retention issues.

Public Health Communication Challenges in an Era of Declining Trust

Copy link to Public Health Communication Challenges in an Era of Declining Trust

The Centers for Disease Control and Prevention (CDC) has defined health communication as “the study and use of communication strategies to inform and influence individual and community decisions that enhance health.”  Public health communication encompasses a broad and long-standing field of research and practice, and in the U.S. communication is recognized as one of the ten Essential Public Health Services and one of the eight Foundational Capabilities for Public Health.

There is a history of successful implementation of communications approaches to improve the public’s health. In the 20th century, for example, there were notable U.S. campaigns to raise awareness about the negative health effects of tobacco use, increase the use of seat belts, and improve nutrition and physical activity, all of which contributed to improved health across the country. 

However, implementing effective public health communication strategies can be difficult, especially in the context of a public health emergency such as an outbreak or pandemic. There is a history of U.S. public health authorities facing communication challenges to combat infectious disease epidemics, including HIV/AIDS and Ebola. More recently many of these same challenges, along with new ones, arose in the context of the COVID-19 pandemic response. 

At present, some key challenges for public health communication in the U.S. include:

  • A “fractured” system of health communicators and sources of health information that includes governmental institutions at the global, federal, state, and local level along with private organizations and individuals, which together can produce an often overwhelming amount of information, not all of which is trustworthy;
  • An evolving set of communication channels for public health information that includes traditional mass media along with a rapidly changing landscape of social media and other online communication networks;
  • A marked decline in trust in health institutions and increased skepticism of expert advice in recent years, as demonstrated in KFF polling;
  • The politicization of public health science and public health messaging, especially during and after the COVID-19 pandemic;
  • More exposure to public health misinformation (the spread of inaccurate or false information) and disinformation (the deliberate spread of false information with the intention to mislead). 

Still, there are strategies that can help address these challenges, such as:

  • Improving coordination on public health messaging among key messengers in public health;
  • Collaborating with information channels such as social media companies to understand and reduce the spread of misinformation;
  • Presenting and disseminating information from trusted sources through multiple channels;
  • Tailoring messages to intended audiences;
  • Engaging in two-way communication that encourages dialogue with members of the public and addresses questions and concerns, especially with those in the “malleable middle” who remain open to updating their opinions on health issues;
  • Proactively countering misinformation and disinformation;
  • Applying continual improvement strategies to learn from successes and failures in public health communication; and
  • Building trusted relationships with communities by engaging consistently over time, rather than only during crises.

Current Topics in U.S. Public Health

Copy link to Current Topics in U.S. Public Health

Case Surveillance, Reportable and Notifiable Diseases

Disease surveillance, which has been defined as the “ongoing, systematic collection, analysis, and interpretation of health-related data,” is a core function of the public health system. This includes collecting case information for diseases of importance, reporting and analyzing that information and investigating it if there is a need. In the U.S., responsibilities for public health surveillance activities are shared among state and local, federal, and private actors, just like for many aspects of public health.

Initial reports on cases of disease may originate from providers such as medical practitioners, hospitals, or laboratories. When a practitioner diagnoses and/or receives a positive lab result for certain conditions, this information is typically reported to the appropriate local and/or state health department, as determined by state disease reporting laws. Such reporting to state and local health departments is mandatory for a specific set of diseases, which are known as reportable diseases. The specific list of reportable diseases – most of which are infectious diseases that can pose a threat to public health – can differ between states, depending upon each jurisdiction's health priorities. Reports to state/local health departments will often include some personally identifiable data on the individual(s) diagnosed, to allow public health authorities to investigate and follow-up. This way, state and local health departments can provide necessary services to affected individuals, and also use reported information to locate the source of potential new outbreaks or health threats and intervene to prevent further spread.

In turn, state and local health departments may also send de-identified data about confirmed cases of certain diseases and conditions that are tracked nationally to the CDC. This notification is voluntary -- the federal government cannot require states to report diseases as that is a public health authority that rests at the state level. CDC does maintain a list of notifiable diseases that it requests state and local health departments provide through its National Notifiable Diseases Surveillance System (NNDSS). This list is updated every year using case definitions refined in collaboration between CDC and Council of State and Territorial Epidemiologists (CSTE). In 2023, for example, there were 123 reportable conditions on CDC’s notifiable diseases list.

Federal Declarations and Powers During Public Health Emergencies

The COVID-19 pandemic demonstrated how consequential public health emergencies can be. It presented the biggest challenge to the U.S. public health system and the largest public health response in a century, and it has had an effect on how public health is practiced across the country. In the event of a threat that is determined to represent a public health emergency, different components of the executive branch can make public health emergency declarations that unlock different flexibilities and resources for response purposes:

  • The President can issue a national emergency declaration pursuant to Section 201 of the National Emergencies Act, which will remain in effect until terminated by the President or through a joint resolution of Congress, or if the President does not issue a continuation notice annually. Such a notice was issued by President Trump for COVID-19 and was extended by President Biden. Declaring a national emergency allows the federal government to waive certain programmatic requirements related to Medicaid and Medicare, among other provisions.
  • The Secretary of HHS can declare a “public health emergency (PHE)” under Section 319 of the Public Health Service Act. A PHE lasts for 90 days and must be renewed to continue, and Congress must be notified of the declaration within 48 hours. Declaring a PHE allows the HHS Secretary the flexibility to take a number of different actions, such as: tap into emergency funds, rapidly approve grants and contracts, waive or modify requirements within health programs such as Medicare and Medicaid, adjust Medicare reimbursement policies for certain drugs, hire new temporary staff and reassign personnel, and other actions. Public health emergency declarations over the past decade have included those for COVID-19, opioids, hurricanes, wildfires, and an epidemic of Zika that began in 2016. 
  • The Secretary of HHS can also make a separate emergency declaration pursuant to Section 564 of the Federal Food, Drug, and Cosmetic (FD&C) Act, which can justify the use of emergency use authorization (EUA) for medical countermeasures needed for emergency response, such as new vaccines, treatments, and/or diagnostics. The EUA mechanism facilitates the availability and use of medical countermeasures determined to be safe and effective, but have not yet been formally approved by FDA. An emergency declaration issued pursuant to Section 564 of the FD&C Act remains in effect until terminated by the HHS Secretary. 

The HHS Secretary can also declare an emergency under the Public Readiness and Emergency Preparedness (PREP) Act (pursuant to Section 319F-3 of the Public Health Service Act), which allows the Secretary to provide liability immunity for companies and other actors for their activities and products developed and implemented to respond to a public health emergency. Such a declaration was made for COVID-19 by the Trump administration and continued by the Biden administration, which provided liability protections for vaccine manufacturers, etc.

Because most public health powers reside at the state level, the federal government has limited ability to issue nationwide mandates related to public health. However, during declared emergencies, the federal government does have expanded powers to do so, though the limits to these powers have been a point of contention during and after the COVID-19 emergency declaration. Examples include:

  • Mandates for federal workers or federal buildings/lands (mask mandate, vaccine mandate)
  • Airline and interstate travel-related mandates (e.g., mask mandates for interstate air, train, or bus travel, contact tracing/information tracking through airlines). A 1944 statute empowers the CDC “to make and enforce such regulations as in [its] judgment are necessary to prevent the introduction, transmission, or spread of communicable diseases from foreign countries into the States . . . or from one State . . . into any other . . . State.”  However, this authority has been the subject of litigation and a federal judge issued a ruling in 2022 that ended the CDC’s mask mandate for public transport during COVID-19.
  • Mandates for immigrants and international visitors (such as quarantine and isolation for incoming air passengers)

Even during emergencies, the federal government does not have the power to mandate widespread business or school closures, or vaccine mandates affecting the country’s population as a whole. State governments (and sometimes local governments), however, do have those authorities, and the federal government can make recommendations for state and local authorities to follow.

Water Fluoridation

Fluoridating water has been a long-standing public health practice in most communities across the U.S. and has been supported and recommended by the federal government for decades. The CDC considers fluoridation to be one of the most important public health interventions ever implemented. However, there has been growing scrutiny of the practice, and debates in many parts of the country about whether to continue fluoridation. Robert F. Kennedy Jr., the Secretary of Health and Human Services in the Trump administration, has long been critical of water fluoridation and has said the Trump administration will recommend that fluoride be removed from public water. Even so, key professional associations, public health experts, and many policymakers continue to support fluoridation as an important tool for improving dental health.

While the federal government does have some role in determining water fluoridation policies nationally, it does not have legal authority to require state and local communities to fluoridate their water, nor to remove fluoridation in areas where it is already policy. Instead, these decisions – just like many public health policy decisions in the U.S. – are made at the state and local levels. There are some states that require water systems of a certain size within their state to provide fluoridated water, while others leave this decision to city, county, or other officials, or leave the choice up to voters who decide via local referendums. At the same time, the federal government – specifically the Environmental Protection Agency (EPA) – does have the primary authority to set and regulate the maximum level of fluoridation in public water systems. In addition, the CDC provides recommendations about best practices for achieving public health benefits from fluoridation that communities may choose to adopt.

Future Outlook

Copy link to Future Outlook

The public health system in the U.S. is a decentralized one, with most authorities and programs delegated to the state and local levels. This “patchwork” system can be a strength and a weakness. While it allows for tailoring public health to more local needs, it also makes more coordinated and uniform action more challenging, particularly in times of emergencies; in addition, public health services and capacity vary significantly across the country, meaning that not all communities have the same level of access and there are resulting inequities in community health status. In addition, while the COVID-19 pandemic brought more attention and funding to public health, it also brought more scrutiny and contributed to a more politicized environment concerning public health, setting up new challenges for its future, including for funding and policy.

The current Trump administration has taken a very different approach to public health compared to the Biden administration. Whereas President Biden oversaw a notable increase in public health investments and expansion of public health efforts during his presidential term, the Trump White House has implemented aggressive cuts to funding, programs, and staff at CDC, FDA, NIH and elsewhere. This includes moves to cut support for federal programs related to diversity, equity, and inclusion (DEI) and racial inequities, and those that address the health needs of LGBTQ+ people. Current HHS Secretary Kennedy stated that “nothing is going to be off limits” when it comes to policy changes at HHS, and so far, he and other staff have initiated a major reorganization, restricted NIH[RS1]  funding for health research, and requested a 25% cut in the department’s budget going forward. Vaccines, a cornerstone of public health efforts and infectious disease control, have been a target for Secretary Kennedy’s policy changes, as he announced new policies and recommendations for COVID-19 vaccines, canceled hundreds of millions of funding for mRNA vaccine research, installed anti-vaccine advocates to key staff positions, dismissed all members of a key federal vaccine advisory committee and hand-selected new members with a history of vaccine skepticism,  and vowed to change a key federal vaccine compensation program underlying the childhood vaccine market. Therefore, public health in the U.S. could be facing a turning point, and the next few years may bring continued turmoil to U.S. public health policy.

Resources

Copy link to Resources

Citation

Copy link to Citation

Michaud, J., Kates, J., Oum, S., & Rouw, A., U.S. Public Health 101. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-u-s-public-health (date accessed).

Poll Finding

KFF Health Tracking Poll: Public Weighs Political Consequences of Health Policy Legislation

Published: Oct 3, 2025

Key Takeaways

  • As Congress debates federal health care spending as part of spending bill negotiations, including extending the enhanced premium tax credits, the latest KFF Health Tracking Poll finds three-quarters (78%) of adults say Congress should extend the enhanced tax credits for people who buy their own insurance through the ACA Marketplace. This is more than three times the share of the public (22%) who say Congress should let the credits expire. Notably, majorities across political party want Congress to extend the tax credits including nine in ten (92%) Democrats, eight in ten (82%) independents, and six in ten (59%) Republicans. A majority of Republicans who align with the MAGA movement (57%) also say Congress should extend these subsidies.
  • Both parties could face political fallout if the enhanced tax credits are not extended, though the public says they will place most of the blame on those currently in charge. About four in ten (39%) adults who want to see the tax credits extended say that if Congress does not extend these enhanced tax credits, President Trump deserves most of the blame, while another four in ten (37%) say the same about Republicans in Congress. About two in ten (22%) say that Democrats in Congress deserve most of the blame. Democrats are most likely to place blame on President Trump (56%) followed by Republicans in Congress (42%), while six in ten Republicans (61%) say they would place the blame on Democrats in Congress. Among those who buy their own coverage (nearly half of whom identify as Republican or Republican-leaning), Republicans in Congress and President Trump receive the majority of the blame (42% and 37%, respectively). 
  • Seven in ten adults who buy their own health insurance say that if the amount they paid for health insurance each month nearly doubled, they could not pay the higher premiums without significantly disrupting their household finances. In addition, four in ten (42%) say they would go without health insurance coverage if the amount they had to pay for health insurance each month nearly doubled. About a third (37%) say they would continue to pay for their current health insurance, while two in ten (22%) would get insurance from another source, like an employer or a spouse’s employer.
  • Majorities across partisanship also report that they would be concerned if they heard about something of the outcomes for both letting the tax credits expire, as well as if Congress extended the tax cuts – granted to a lesser degree. Majorities say they would be concerned if they heard that health insurance would be unaffordable for many people who buy their own coverage (86%), that 4 million people would lose their health insurance coverage (86%), or if they heard that people who work at small businesses or are self-employed would be directly impacted (85%). On the other side, if Congress does extend these enhanced tax credits, two-thirds of the public (63%) say they would be concerned if they heard that it would require significant federal spending that would be largely paid for by taxpayers.
  • Three months after the passing of the tax and budget legislation, the bill still remains largely unfavorable among the public overall – lagging far behind both the Affordable Care Act and the ACA Marketplaces in overall popularity. Many are still unsure of how the legislation will impact them personally but four in ten (43%) think it’s most likely to hurt them and their families.

Public Still Largely Unaware That ACA Enhanced Tax Credits Are Expiring, Strong Support for Congress Extending Them

On October 1st the U.S. federal government shut down as Congress was unable to pass a stopgap spending bill. As part of the discussions around the federal budget, Democrats are seeking to include the extension of the enhanced premium tax credits (ePTCs) for people who purchase their own health insurance through the ACA Marketplace that are set to expire at the end of the year.

About six in ten adults say they have heard “a little” (30%) or “nothing at all” (31%) about the expiring ACA subsidies, showing widespread lack of information on the cost of coverage for over 24 million people in the U.S.  Four in ten say (39%) they’ve heard “a lot” or “some” – up from 27% in June of this year. Even among the group whose cost of coverage is expected to double next year – those who purchase their own insurance plans – about six in ten (58%) say they have heard just “a little” or “nothing at all” about the expiration of tax credits for people who self-purchased insurance.

Democrats seem to be more aware of the pending expiration, with about half of Democrats (50%) saying they have heard at least “some” about this, compared to about a third of independents (35%) and Republicans (34%).

Stacked bar chart showing the levels of public awareness about the enhanced ACA marketplace subsidies.

Once the public is told that the expiration date for subsidies is looming, about three-quarters (78%) of adults say Congress should extend the enhanced tax credits for people who buy their own insurance through the ACA Marketplace, more than three times the share (22%) who say Congress should let the credits expire. Over eight in ten (84%) of those who buy their own insurance say that Congress should extend the enhanced tax credits.

Although Republicans are more likely than Democrats and independents to say that Congress should let the credits expire, majorities across political party want Congress to extend the tax credits including nine in ten (92%) Democrats, eight in ten (82%) independents, and six in ten (59%) Republicans, including 57% of Republicans who align with the MAGA movement. 

Split bar chart showing the shares of adults who say the enhanced marketplace tax credits should be extended and those who say they should be allowed to expire.

Previous KFF polling has shown that attitudes towards the credits shift slightly after hearing counterarguments both for and against the extension of the credits. This month’s poll shows that large majorities of the public, including majorities of Democrats, independents, Republicans, and MAGA supporters are concerned about many of the potential consequences of letting these enhanced tax credits expire. Additionally, majorities of independents and Republicans and about half of Democrats are concerned about the consequences for extending them.

More than eight in ten adults say they would be concerned, including at least half who say they would be “very concerned,” if they heard that health insurance would be unaffordable for many people who buy their own coverage (86%), that 4 million people would lose their health insurance coverage (86%), or if they heard that people who work at small businesses or are self-employed would be directly impacted (85%).

Stacked bar charts showing the level of concern adults would have if they heard about impacts of letting the ACA marketplace tax credits expire.

Concern over the possible consequences is high across party lines with large majorities of Democrats and independents saying they would be concerned about each of these potential outcomes, as well as three-quarters of Republicans and MAGA supporters.

Split bar chart showing shares by party who say they would be very or somewhat concerned to hear about impacts of letting ACA marketplace tax credits expire.

On the other side, if Congress does extend these enhanced tax credits, two-thirds (63%) of the public say they would be concerned if they heard that it would require significant federal spending that would be largely paid for by taxpayers, including a quarter (27%) who would be “very concerned.” This is predictably divided along partisan lines. More than eight in ten (83%) Republicans say they would be concerned about federal spending, but notably so do more than six in ten independents (61%) and nearly half of Democrats (49%). Republicans who support the MAGA movement are among the most worried about this issue, with almost half (47%) saying they would be “very concerned.”  

Stacked bar chart showing the levels of concern adults would have about federal spending if ACA marketplace tax credits were extended.

The poll finds more people say they would blame President Trump or Republicans in Congress than Democrats if tax credits are not extended. About four in ten (39%) adults who want to see the tax credits extended say that if Congress does not extend these enhanced tax credits, President Trump deserves most of the blame, while another four in ten (37%) say the same about Republicans in Congress. About two in ten (22%) say that Democrats in Congress deserve most of the blame, driven heavily by Republicans. Six in ten (61%) Republicans who want to see the tax credits extended say they would blame Democrats in Congress, including seven in ten MAGA Republicans, compared to one in six (17%) independents.

Over half of Democrats (56%) who want to see the tax credits extended say that if they are not extended, President Trump deserves most of the blame, though four in ten (42%) blame Republicans in Congress. Independents are largely split, with about four in ten saying they will blame Republicans in Congress (42%) or President Trump (39%).

Adults who purchased their own insurance, most of whom do so through the ACA Marketplace, are similarly split, with four in ten (42%) placing the blame if Congress does not extend the enhanced tax credits on Republicans in Congress and four in ten (37%) on President Trump. Two in ten (21%) of this group would blame Democrats in Congress if the subsidies expire. Notably, a previous KFF poll found that nearly half of adults enrolled in ACA Marketplace plans identify as Republican or lean Republican.

Stacked bar chart showing who the public would blame if Congress does not extend these enhanced tax credits.

Marketplace Enrollees Unsure How to Afford Coverage if Enhanced Tax Credits Expire

Six in ten adults who buy their own health insurance coverage think the cost of their personal health insurance would increase at least “some” if the tax credits are not extended, while about a quarter say they think it will increase “a little” (24%), or that their costs won’t increase at all (15%). Estimates are that the amount enrollees pay for premiums for ACA Marketplace plans will more than double on average and nearly 4 million people could eventually be uninsured. Notably, more than half of adults with Medicaid (54%) also say they think that if the enhanced tax credits expire the cost of their own coverage will also increase at least “some,” as do about four in ten people with Medicare age 65 and older and about half of people with employer-sponsored insurance.  It is important to note that the expiration of enhanced tax credits only directly impact people who buy their own coverage on the ACA Marketplace.

Stacked bar chart showing how much people who buy their own insurance think their health coverage will increase if the enhanced tax credits expire.

Among those who have insurance through the ACA Marketplace, seven in ten say that if the amount they paid for health insurance each month nearly doubled, they could not pay the higher premiums without significantly disrupting their household finances. Just three in ten estimate that they could pay the higher premiums.

Split bar chart showing the share of people with self-purchased insurance who say they would or would not be able to afford higher premiums if their coverage nearly doubled.

About four in ten (42%) Marketplace enrollees say they would go without health insurance coverage if the amount they had to pay for health insurance each month nearly doubled. Just over a third (37%) say they would continue to pay for their current health insurance, while about a quarter (22%) would get insurance from another source, like an employer or a spouse’s employer.

Stacked bar chart showing what the share of the public with self-purchased insurance would do if their health insurance nearly doubled.

Public Views of Major Health Care Legislation

On July 4, 2025, President Trump signed a sweeping legislative package known as the “Big Beautiful Bill,” that included significant changes to the country’s Medicaid program and the Affordable Care Act (ACA) Marketplaces. The package, which passed on a party-line vote, with no Democrats in favor, has been described as the biggest rollback of the country’s health care programs in modern history. Now, as part of federal budget negotiations, Democrats in Congress, are seeking to minimize some of these health insurance rollbacks. The latest KFF Health Tracking Poll shows both parties are playing to their bases, with Republicans strongly supporting the “Big Beautiful Bill” (BBB) legislation and Democrats largely opposed.

Overall, about four in ten (38%) adults hold favorable views of the tax and budget legislation passed earlier this year, including three-quarters of Republicans (75%) and eight in ten (82%) Republicans or Republican-leaning independents who support the MAGA movement. Democrats and independents, on the other hand, largely hold unfavorable views of the legislation, including nearly nine in ten (88%) Democrats and two-thirds (68%) of independents who say they view the law unfavorably.

Split bar chart showing the share of the public who have a favorable or unfavorable view of the "big beautiful bill".

The share of the public who say they have a favorable opinion of the tax and budget legislation has stayed relatively stable, at close to four in ten (38%), similar to 36% in July and 35% in June.

Overall favorability of the 2010 health care law known as the Affordable Care Act (ACA) continues to be at historically high levels, with about two-thirds (64%) of the public viewing the law positively. This is largely driven by Democrats and independents, with over nine in ten (94%) Democrats and two-thirds (64%) of independents viewing the law favorably, while two-thirds (64%) of Republicans have an unfavorable view. Click here to explore more than ten years of polling on the ACA.

Majorities Across Partisans View ACA Marketplaces Favorably

The ACA Marketplaces where people and small businesses can shop for health insurance are even more popular than the ACA itself, with seven in ten (70%) adults having a favorable view. The ACA Marketplaces have consistently been a more popular provision of the ACA, even before Congress passed the American Rescue Plan Act (ARPA) in 2021, which provided temporarily enhanced tax credits to adults who purchased their own health insurance through the Marketplaces. Though views of the ACA Marketplace are divided by partisanship, majorities across party lines view the ACA Marketplace positively, with eight in ten (84%) Democrats, seven in ten (69%) independents, and six in ten (59%) Republicans holding a favorable view. This also includes MAGA Republicans and Republican-leaning independents, among whom over half (56%) hold a favorable opinion of the Marketplace.

Among those who purchase their health care plan themselves, many of whom bought through the ACA Marketplace, seven in ten have a favorable opinion of the ACA health insurance exchanges or Marketplaces.

Stacked bar chart showing the public's level of favorability toward the ACA marketplaces.

Many Still Unsure How the “Big Beautiful Bill” Will Impact Them

Three months after the passing of President Trump’s major legislative achievement, the “Big Beautiful Bill,” most people remain unaware of how the effects of the tax and budget legislation will impact them. Six in ten adults say they do not have enough information as to how the legislation will impact them personally, while four in ten report that they do have enough information.

Democrats (50%) are more likely than Republicans (36%) and independents (37%) to say they have enough information about how the BBB will impact them personally. About four in ten (41%) Republicans and Republican-leaning independents who identify with the MAGA movement say they have enough information about the impact of the legislation, though majorities (59%) still do not.

The BBB legislation has made changes to the ACA Marketplaces including limiting some eligibility and shortening the open enrollment period. Among those who purchase their own health insurance, two-thirds (63%) say they do not have enough information about how the legislation will impact them. 

Split bar chart showing the share of adults who say they either have enough information or not enough information about the "big beautiful bill".

While many say they don’t have enough information about how the tax and budget legislation will affect them, partisanship once again plays a major role in public perception of the law’s impact. About four in ten (43%) say the recent legislation will generally hurt them and their families, which is twice the share who say the legislation will generally help them. More than a third of the public (36%) say the law won’t make a difference to them and their families.

Two-thirds (68%) of Democrats say the tax and budget legislation will generally hurt them and their families, as do about half (48%) of independents. Republicans are split between thinking the law will help them and thinking it won’t make a difference, with similar shares saying the law will help them and their families (43%) and saying they don’t think the law will make a difference for them (46%). Nearly half of Republicans and leaners who support the MAGA movement say the law will help them (48%) while four in ten say it won’t make a difference for them. Very few MAGA supporters (11%) say the law will hurt them.

Among those who purchase their own insurance, many through the ACA Marketplace, four in ten (42%) expect the legislation will generally hurt them and their family, while similar share (37%) expects it to not make much of a difference and just one in five (19%) say it will help.

Stacked bar chart showing the share of the public's views on how the big beautiful bill will impact them and their family.

This KFF Health Tracking Poll was designed and analyzed by public opinion researchers at KFF. The survey was conducted September 23-29, 2025, online and by telephone among a nationally representative sample of 1,334 U.S. adults in English (n=1,255) and in Spanish (n=79). The sample includes 1,026 adults (n=64 in Spanish) reached through the SSRS Opinion Panel either online (n=1,004) or over the phone (n=22). The SSRS Opinion Panel is a nationally representative probability-based panel where panel members are recruited randomly in one of two ways: (a) Through invitations mailed to respondents randomly sampled from an Address-Based Sample (ABS) provided by Marketing Systems Groups (MSG) through the U.S. Postal Service’s Computerized Delivery Sequence (CDS); (b) from a dual-frame random digit dial (RDD) sample provided by MSG. For the online panel component, invitations were sent to panel members by email followed by up to three reminder emails. 

Another 308 (n=15  in Spanish) adults were reached through random digit dial telephone sample of prepaid cell phone numbers obtained through MSG. Phone numbers used for the prepaid cell phone component were randomly generated from a cell phone sampling frame with disproportionate stratification aimed at reaching Hispanic and non-Hispanic Black respondents. Stratification was based on incidence of the race/ethnicity groups within each frame. Among this prepaid cell phone component, 141 were interviewed by phone and 167 were invited to the web survey via short message service (SMS). 

Respondents in the prepaid cell phone sample who were interviewed by phone received a $15 incentive via a check received by mail. Respondents in the prepaid cell phone sample reached via SMS received a $10 electronic gift card incentive. SSRS Opinion Panel respondents received a $5 electronic gift card incentive (some harder-to-reach groups received a $10 electronic gift card). In order to ensure data quality, cases were removed if they failed two or more quality checks: (1) attention check questions in the online version of the questionnaire, (2) had over 30% item non-response, or (3) had a length less than one quarter of the mean length by mode. Based on this criterion, no cases were removed.

The combined cell phone and panel samples were weighted to match the sample’s demographics to the national U.S. adult population using data from the Census Bureau’s 2024 Current Population Survey (CPS), September 2023 Volunteering and Civic Life Supplement data from the CPS, and the 2025 KFF Benchmarking Survey with ABS and prepaid cell phone samples. The demographic variables included in weighting for the general population sample are gender, age, education, race/ethnicity, region, civic engagement, frequency of internet use, and political party identification. The weights account for differences in the probability of selection for each sample type (prepaid cell phone and panel). This includes adjustment for the sample design and geographic stratification of the cell phone sample, within household probability of selection, and the design of the panel-recruitment procedure.

The margin of sampling error including the design effect for the full sample is plus or minus 3 percentage points. Numbers of respondents and margins of sampling error for key subgroups are shown in the table below. For results based on other subgroups, the margin of sampling error may be higher. Sample sizes and margins of sampling error for other subgroups are available on request. Sampling error is only one of many potential sources of error and there may be other unmeasured error in this or any other public opinion poll. KFF public opinion and survey research is a charter member of the Transparency Initiative of the American Association for Public Opinion Research. 

GroupN (unweighted)M.O.S.E.
Total1,334± 3 percentage points
Party ID
Democrats418± 6 percentage points
Independents455± 6 percentage points
Republicans385± 6 percentage points
MAGA Republicans374± 6 percentage points


News Release

Despite Budget Concerns, Three-Quarters of Public Say Congress Should Extend the Enhanced ACA Tax Credits Set to Expire Next Year, Including Most Republicans and MAGA Supporters

7 in 10 Marketplace Enrollees Say They Could Not Afford Coverage if Their Premiums Doubled; 4 in 10 Say They Would Expect to Be Uninsured

Published: Oct 3, 2025

More than three-quarters (78%) of the public say they want Congress to extend the enhanced tax credits available to people with low and moderate incomes to make the health coverage purchased through the Affordable Care Act’s Marketplace more affordable, a new KFF Health Tracking Poll finds. That’s more than three times the share (22%) who say they want Congress to let the tax credits expire.

Most Republicans (59%) and “Make American Great Again” supporters (57%) favor extending the enhanced tax credits, which otherwise would expire at the end of the year and require Marketplace customers to pay much more in premiums to retain coverage. Larger majorities of Democrats (92%) and independents (82%) also support extending the enhanced tax credits, as do most people who buy their own health insurance, most of whom purchase through the Marketplace (84%).

The poll also tests the public’s response to arguments made by those who support and oppose extending the enhanced tax credits.

Among the public overall, more than eight in 10 say they would be concerned about the expirations of the tax credits if they heard that health insurance would become unaffordable for many people who buy their own coverage (86%), that about 4 million people would lose their health insurance coverage (86%), or that millions of people who work at small businesses or are self-employed would be directly impacted because they rely on the ACA Marketplace (85%).

In the other direction, a smaller majority (63%) say they would be concerned about extending the enhanced tax credits if they heard that it would require significant federal spending that would largely be paid by taxpayers. This includes a large majority of Republicans (83%) and most independents (61%).

When people who want to extend the enhanced tax credits were asked who deserves the most blame if they expire, roughly equal shares say President Trump (39%) and Republicans in Congress (37%), while a smaller share (22%) say that Democrats in Congress would deserve most of the blame.

“There is a hot debate in Washington about the looming ACA premium hikes, but our poll shows that most people in the marketplaces don’t know about them yet and are in for a shock when they learn about them in November,” KFF President and CEO Drew Altman said.

The poll was fielded just prior to the Oct. 1 federal government shutdown that was triggered in part by disagreements about whether, how and when to extend the expiring tax credits. A recent KFF analysis finds that losing that extra help would increase what Marketplace enrollees receiving financial assistance pay in premiums by an average of 114% – from $888 in 2025 to $1,904 next year.

The poll suggests that many Marketplace enrollees are going to be surprised by the jump in their premiums if the tax credits aren’t renewed in time for 2026 open enrollment period, which starts Nov. 1.

Among people who buy their own coverage (largely through the Marketplaces), about six in ten (58%) say they have heard just “a little” or “nothing at all” about the expiration of tax credits for eligible people with Marketplace coverage.

Among those who buy their own insurance, about a third (35%) expect their premiums to increase “a lot” next year.  A quarter (25%) expect their premiums to rise “some,” another quarter (24%) expect their premiums to increase “a little,” and the rest (15%) don’t expect any increase.

When asked if they could afford health coverage if their premiums nearly doubled, seven in 10 (70%) of those who purchase their own insurance say they would not be able to afford the premiums without significantly disrupting their household finances, more than twice the share (30%) who say they could afford the higher premiums.

About four in 10 (42%) Marketplace enrollees say they would go without health insurance coverage if the amount they had to pay for health insurance each month nearly doubled. Similar shares (37%) say they would continue to pay for their current health insurance, while two in 10 (22%) say they would get insurance from another source, like an employer or a spouse’s employer.

Other findings include:

  • Nearly two thirds (64%) of the public continue to hold favorable views of the Affordable Care Act overall, and a somewhat larger majority (70%) holds favorable views of the ACA’s Marketplaces. While two thirds (64%) of Republicans view the overall ACA unfavorably, most (59%) view the ACA Marketplaces themselves favorably.
  • Most (61%) of the public holds unfavorable views of the tax and budget law enacted in July, also known as the “big beautiful bill,” while about four in 10 (38%) view it favorably. Large majorities of Democrats (88%) and independents (68%) view the law unfavorably, while similar majorities of Republicans (75%) and MAGA supporters (82%) view it favorably.

Designed and analyzed by public opinion researchers at KFF, this survey was conducted September 23-29, 2025, online and by telephone among a nationally representative sample of 1,334 U.S. adults in English and in Spanish. The margin of sampling error is plus or minus 3 percentage points for the full sample. For results based on other subgroups, the margin of sampling error may be higher.

Health Policy Issues in Women’s Health

Table of Contents

Introduction

Copy link to Introduction

Health care is a central element of women’s lives, shaping their ability to care for themselves and their families, to be productive members of their communities, to contribute to the workforce, and to build a base of economic security. Women’s reproductive health care needs, their central roles managing family health as parents and as family caregivers, and their longer lifespans, albeit with greater rates of chronic health problems and functional limitations than men, all shape their relationships with the health care system. While women are major consumers of health care services and play a central role as health navigators and caregivers for their families, structural factors can challenge their ability to get the health care they need. Factors, including national and state policies that shape the health care delivery system to research priorities and discriminatory economic and societal forces, can deprioritize women’s health concerns. Access challenges are greater for women who are in low-income households, who face structural and societal racism and discrimination, who struggle with complex or understudied medical conditions, or who live in states or communities that have enacted or invested in policies and programs that do not support their health needs.

In the United States, the women’s health movement gained significant traction in the 1960s and 1970s as part of a larger grassroots women’s rights movement that challenged long-standing inequities and discrimination that limited women’s economic and social opportunities. The book, “Our Bodies, Ourselves,” brought a wide range of women’s health concerns, ranging from abortion and sexuality to menopause and cancer, into the mainstream. Over time, federal action also began to address many of the long-standing discriminatory sex and gender-based policies that were baked into our employment, health, and research policies. The 1973 U.S. Supreme Court ruling in Roe v. Wade decriminalized and protected the right to abortion care for nearly 50 years; the Pregnancy Discrimination Act of 1978 offered workplace and insurance protections to pregnant workers; the National Institutes of Health (NIH) Revitalization Act of 1993 mandated the inclusion of women in clinical research and formally established the NIH Office of Women’s Health; and in 2010, the Affordable Care Act (ACA) banned many of the discriminatory practices that had shaped women’s coverage of and access to care. While many of these policy changes have resulted in improvements and advances in women’s health, including access and coverage, the advances have not been linear.  In 2022, the Supreme Court, with a conservative supermajority, struck down the right to abortion in Dobbs v Jackson Women’s Health, resulting in the outright banning of abortion in many states. Despite advances in women’s health research, many gaps remain and the Trump Administration has targeted and blocked federal funding that focuses on gender, a pillar of women’s health research.     

This primer focuses on some of the key areas disproportionately affecting women today that are shaped by national and state health policies. This includes health coverage and costs, reproductive health services, maternal health, mental health, and intimate partner violence. In addition, it highlights some of the structural factors and inequities that still impact women’s health, particularly women of color and gender-expansive individuals such as those who are transgender or non-binary or otherwise gender fluid or non-conforming who are at risk of being marginalized or discriminated against by their health coverage or providers. We note that while we refer to “women” and “women’s health” throughout this chapter, some persons assigned female sex at birth do not identify as women, such as transgender men, non-binary individuals, and otherwise gender-expansive individuals. Still, many of the issues discussed in this chapter also apply to them.

What Is the Demographic Profile of Women?

Copy link to What Is the Demographic Profile of Women?

More than 128 million adult women over the age of 19 live in the U.S. today, with great diversity in many demographic characteristics. A third of adult women are between the ages of 35-54 (33%) and the majority are White (60%) (Figure 1). Nearly 1 in 5 (17%) women are Hispanic, 12% are Black and 6% are Asian.

Almost two-thirds (65%) of women live in a household with at least one full-time worker, while 1 in 10 (9%) live in a household with only part-time workers, and 25% of women live in households with no workers (data not shown). Given the important role of employment in shaping health coverage, workforce participation is a significant determinant of the type of health insurance that working women or women who live in households with full-time workers can obtain.

While most women in the U.S. report having good health, nearly 1 in 5 (18%) women 18 and older rate their health as “fair” or “poor” and 14% report having a disability such as difficulty with vision, hearing, or walking. As women age, they are more likely to experience chronic health problems and declines in health status. These factors are highly predictive of their need for and use of health care services.

Income also plays a major role in health coverage and access to care. Income affects the resources that women have to pay for out-of-pocket health care costs and contribute to premium costs. Income also determines women’s eligibility for programs such as Medicaid or subsidies to secure coverage through the ACA Marketplace. Almost three in 10 (28%) adult women are part of households with low incomes (family income below 200% of the FPL was $49,720 for a family of three in 2023). Almost 4 in 10 (36%) women have completed a bachelor’s degree or higher, almost a third (27%) have a child under the age of 19 living at home, and 92% are U.S. citizens. Nearly 4 in 10 women live in the South (39%), almost a quarter (23%) live in the West, a fifth (20%) live in the Midwest, and 17% live in the Northeast (Figure 2).

What Are the Sources of Health Insurance Coverage for Women?

Copy link to What Are the Sources of Health Insurance Coverage for Women?

While most adult women have some form of either private or public health insurance, the coverage profile for those who are under and over age 65 differs considerably. For those who are under age 65, employer-sponsored coverage, individually purchased policies, and Medicaid—the state-federal program for people with low incomes—comprise the majority of coverage options. However, nearly 1 in 10 women in that age group are currently uninsured. Among women 65 years and older, the Medicare program plays a critical role covering nearly all seniors in the U.S., though often with considerable coverage gaps (such as hearing, vision and long-term services and supports) and cost-sharing burdens.

Employer-Sponsored Insurance

Approximately 58.3 million women aged 19-64 (60%) received their health coverage from employer-sponsored insurance in 2023 (Figure 3). Women in families with at least one full-time worker are more likely to have job-based coverage (70%) than women in families with only part-time workers (33%) or without any workers (17%).

Employer-sponsored insurance can come with substantial out-of-pocket costs based on premiums, deductibles, co-insurance, and co-payment levels. In 2023, annual insurance premiums for employer-sponsored insurance averaged $8,435 for individuals and $23,968 for families. On average, workers paid 17% of premiums for individual coverage and 29% for family coverage with the employers picking up the balance.

Women's Health Insurance Coverage, 2023 (Donut Chart)

Non-Group Insurance

In 2023, about 9% of women ages 19 to 64 (approximately 8.4 million women) and 8% of their male counterparts purchased insurance in the non-group market. This includes individuals who purchased private policies from state-based Marketplaces established under the ACA, as well as those who purchased coverage from private insurers that operate outside of the ACA Marketplaces.

Most individuals who seek insurance policies in their state’s Marketplace qualify for assistance with the coverage costs. Individuals with incomes below $58,320 (400% of the Federal Poverty Level in 2023) can receive federal tax credits which lower premium costs. The American Rescue Act (ARPA) of 2021, and subsequently the Inflation Reduction Act of 2022, have provided a temporary extension of Marketplace subsidies to people with higher income levels and led to record high enrollments in the ACA marketplace. These subsidies are set to expire at the end of 2025 and if they are not renewed, it would lead to a steep increase in insurance premium payments for ACA Marketplace enrollees. 

The ACA set new standards for all individually purchased plans and eliminated many historically discriminatory practices that affected disadvantaged women in particular. Today, plans are prohibited from charging women higher premiums than men for the same level of coverage (gender rating) or from disqualifying women from coverage because they had certain pre-existing medical conditions, including pregnancy. All direct purchase plans must also cover certain “essential health benefits” (EHBs) that fall under 10 different categories, including maternity and newborn care, mental health, and a wide range of preventive health care services. Prior to the ACA, many individual plans excluded maternity care benefits or required policyholders to purchase costly riders to obtain maternity coverage.

Medicaid

Medicaid, the state-federal program for individuals with low incomes, covered 19% of adult women ages 19 to 64 in 2023, compared to 14% of men. Historically, to qualify for Medicaid, women had to have very low incomes and be in one of Medicaid’s eligibility categories: pregnant, mothers of children 18 and younger, a person with a disability, or over 65. Women who didn’t fall into these categories typically were not eligible regardless of how low their incomes were. The ACA allowed states to broaden Medicaid eligibility to most individuals with incomes less than 138% of the FPL regardless of their family or disability status, effective January 2014. As of April 2025, 40 states and Washington, D.C. have expanded their Medicaid programs under the ACA, but 10 states have not and still base eligibility on historical categorical and income standards. For example, in Mississippi, the Medicaid income eligibility for parents is 28% of the FPL, which was approximately $6,900 for a family of three in 2023. Therefore, parents in families of three in Mississippi with incomes above this amount do not qualify for Medicaid because their income exceeds the state’s eligibility level.

Medicaid covers the poorest segment of women in the U.S. Forty-four percent of women with incomes below 200% of the FPL and 52% of women with incomes below 100% of the FPL have Medicaid coverage.By federal law, all states must provide Medicaid coverage to pregnant women with incomes up to 133% of the FPL through 60 days postpartum. However, in recent years, there has been a growing interest in expanding the length of the postpartum coverage period and, as of April 2025, nearly all states have taken steps to extend postpartum Medicaid coverage to one year.

Medicaid covers many health services that are essential for women. Medicaid financed 41% of births in the U.S. in 2022 and accounts for 75% of all publicly-funded family planning services. State Medicaid programs are prohibited from charging any cost-sharing for pregnancy-related care or family planning services. Over half of states have established programs that use Medicaid funds to cover the costs of family planning services for women with low incomes who remain uninsured, and most states have limited scope Medicaid programs to pay for breast and cervical cancer treatment for certain uninsured women with low incomes. Conversely, coverage for abortion is very limited under Medicaid as a result of the Hyde Amendment, a rider to federal appropriations that bans any federal funds from being used to pay for abortions unless the pregnancy is determined to be a result of rape or incest or poses a threat to the pregnant person’s life (more on abortion in the following section).

Uninsured Women

In 2023, approximately 10% of non-elderly women (9.3 million) were uninsured. This rate is slightly lower than that of men (13%) because, on average, women have lower incomes and have been more likely to qualify for Medicaid than men under one of Medicaid’s eligibility categories: pregnant, parent of children under 18, disability, or over 65. The ACA opened the door for states to eliminate the categorical requirements, but the gender gap in the insured rates between men and women persists.

The disadvantage uninsured individuals experience in accessing care and health outcomes is well established. Compared to women with insurance, those who are uninsured have lower use of important preventive services such as mammograms, Pap tests, and timely blood pressure checks. They are also less likely to report having a regular doctor, which is associated with better access to care and higher rates of use of recommended preventive services.

Women with lower incomes, women of color, and non-citizen women are at greater risk of being uninsured (Figure 4). One in 5 Hispanic (20%) and American Indian and Alaska Native (19%) women and 17% of women with incomes under 200% of the FPL are uninsured. A higher share of single mothers are uninsured (10%) than women in two-parent households (7%) (data not shown). Most uninsured women live in a household where someone is working; 69% are in families with at least one adult working full-time; and 82% are in families with at least one part-time or full-time worker (data not shown).

Health Insurance Coverage Among Non-Elderly Women by Selected Characteristics, 2023 (Stacked Bars)

Many women who are uninsured are eligible for financial assistance with the costs of coverage. A fifth of uninsured women (20%) are eligible for Medicaid coverage but are not enrolled in the program (Figure 5). Over a third of uninsured women (36%), about 3.3 million women, qualify for subsidies to cover the premium costs and some of the out-of-pocket costs of Marketplace plans but may not be aware of coverage options or may face barriers to enrollment. However, 7% of uninsured women live in states that have not adopted the ACA Medicaid expansion and fall into a “coverage gap” because their incomes are above the thresholds to qualify for Medicaid but below the levels to qualify for Marketplace tax credits (below 100% of the FPL). Another 1 in 3 (37%) uninsured women are not eligible for any assistance with health coverage due to their immigration status, their income, or because they have an offer of coverage from their employer.

Eligibility for Assistance under the ACA Among Uninsured Women Ages 19-64, 2023

There is considerable state-level variation in uninsured rates across the nation, ranging from 20% of women in Texas to 3% of women in Washington D.C., Hawaii, Massachusetts, and Vermont (Figure 6). Of the 16 states with uninsured rates above the national average (10%), eight have not adopted the ACA Medicaid expansion.

Uninsured Rates Among Women Ages 19 to 64, by State, 2023 (Choropleth map)

Medicare

Medicare is the federal program that provides health coverage to virtually all people ages 65 and older as well as younger people with long-term disabilities. In 2020, Medicare covered 35 million women, including nearly 31 million ages 65 and older, and over 4 million under age 65 with long-term disabilities.

More than half (55%) of all Medicare beneficiaries are women and 45% are men. The population of women covered by Medicare is diverse, with varying social, economic, and health circumstances. Women live longer than men on average (80 years vs. 75 years life expectancy at birth in 2022), and many live with certain chronic illnesses, cognitive and mental impairments, and functional problems at higher rates than men. A higher share of older women than men also experience urinary incontinence, depression, osteoporosis, pulmonary disease, and Alzheimer’s/dementia. Medicare plays a key role in supporting the health and well-being of women, covering a broad range of essential services, including preventive, primary and specialty care, and prescription drugs. However, reflecting Medicare’s original role as a program to serve the medical needs of older adults, coverage of services for enrollees of reproductive age may be more limited. For example, there is no federal requirement for Medicare to cover all contraceptive services and supplies for the purpose of preventing pregnancy for younger Medicare enrollees with permanent disabilities.

Another gap in the Medicare program is the absence of coverage for long-term care services and supports (LTSS), such as nursing home stays and home care services, which many older adults need and seek but are expensive and unaffordable for some. Compared with men, women are more likely to require these services because they have more chronic conditions, have higher rates of physical and cognitive impairments, and are more likely to live alone. Medicare only covers time-limited LTSS after a hospitalization and does not cover ongoing LTSS for those with chronic conditions or functional impairments. Some older women can qualify for Medicaid for LTSS, but only if they have low incomes and, in some cases, must spend down most of their assets. Just a small share of seniors have private long-term care insurance to help cover some of the costs of LTSS. As a result, unless they have incomes low enough to qualify for Medicaid, many older people do not have any coverage for LTSS and rely on unpaid caregiving provided by family, friends, or neighbors. The majority of informal caregivers are women, who are most commonly caring for aging parents and spouses.

Women with Medicare also tend to have more modest incomes than men—a consequence of smaller lifetime savings, lower retirement income, and divorce and widowhood that result in only one income. While Medicare covers many necessary health care services, gaps in benefits, cost-sharing requirements, and spending on premiums for Medicare and supplemental coverage can translate into high out-of-pocket expenses for some people in the program. In 2020, 13% of women and 11% of men with Medicare reported that they had faced cost-related challenges in the past 12 months, such as trouble getting care due to cost or problems paying medical bills. These challenges are more common among female Medicare enrollees who are Black (22%) and Hispanic (18%), do not have a bachelor’s degree (15%), and those with annual incomes below $20,000 (20%).

How Do Health Care Costs and Scope of Benefits Affect Women’s Access to Care?

Copy link to How Do Health Care Costs and Scope of Benefits Affect Women’s Access to Care?

The ACA set national standards for the scope of benefits offered in private plans. As mentioned earlier, many insurance plans had adopted practices that discriminated against women that were addressed in the ACA. In addition to the broad categories of essential health benefits (EHBs) offered by Marketplace plans, all privately purchased plans must cover maternity care, which had been historically excluded from most individually purchased plans requiring the purchase of an expensive rider for that benefit to be covered. In addition, most private plans must cover preventive services without co-payments or other cost sharing. This includes screenings for breast and cervical cancers, well-woman visits (including prenatal visits), prescribed contraceptives, breastfeeding supplies and supports such as breast pumps, and several services for sexually transmitted infections (STI). Higher shares of women with private and Medicaid coverage report having had recommended preventive services such as mammograms, Pap screenings or colonoscopies compared to those who were uninsured (Figure 7).

Share of women who have had a mammogram, cervical cancer screening, or colon cancer screening in the past two years

Affordability of coverage continues to be a significant concern for many women, both for those who are uninsured as well as those with coverage. The leading reason why uninsured adults report that they have not obtained coverage is that it is too expensive. Under employer-sponsored insurance, the major source of coverage for women, 61% of all covered workers with a general annual deductible have deductibles of at least $1,000 for single coverage. Despite having coverage, many insured women (31%) report that their plans did not always cover all of their needed care or paid less than they expected (Figure 8).

Share of Insured Women 18-64 Who Experienced Problems Using their Health Insurance in the Past 12 Months (Grouped column chart)

What Are the Issues Affecting Women's Care and Access?

Copy link to What Are the Issues Affecting Women's Care and Access?

Reproductive Health

Pregnancy

Maternity Care

In 2023, there were approximately 3.6 million births in the U.S. Childbirth is the leading reason for hospitalization, and most private insurance plans and the Medicaid program are required to cover care associated with childbirth. Medicaid covers about 4 in 10 births nationally and, in some states, more than half. The Medicaid program prohibits plans from charging out-of-pocket charges for pregnancy-related care, and coverage lasts through one year postpartum in most, but not all, states. For people with private insurance, which finances just over half of  births (51%), the federal Pregnancy Discrimination Act requires employer plans to cover maternity care benefits. However, even for those with private insurance, a pregnancy often comes with significant out-of-pocket health expenses that can reach thousands of dollars. A KFF analysis estimated that women enrolled in large group plans pay around $3,000 out-of-pocket for costs associated with pregnancy, childbirth, and post-partum care. On average, Caesarean section births, which account for approximately one-third of births in the U.S., are significantly more expensive than vaginal deliveries. The ACA also requires individual plans to cover maternity care and bans plans from implementing restrictions on coverage of pre-existing health conditions, including pregnancy.

In recent years, there has been growing attention to pregnancy-related quality of care and maternal health. Maternal and infant mortality rates in the U.S. are far higher than those in similarly large and developed countries, and people of color are at a considerably higher risk for poor maternal and infant health outcomes compared to their White peers. Despite continued advancements in medical care, rates of maternal mortality and morbidity and preterm birth have been rising in the U.S., characterized by stark racial disparities. Notably, rates of pregnancy-related death (deaths within one year of pregnancy) among American Indian and Alaska Native (AIAN), Native Hawaiian or Pacific Islander (NHPI) and Black women are over four to two times higher, respectively, compared to the rate for White women (118.7, 111.7, 69.3 and 24.3 per 100,000 live births, respectively) (Figure 9). The Centers for Disease Control (CDC) has determined that many of these pregnancy-related deaths were preventable, caused by cardiac-related conditions, infection, hemorrhage, and mental health conditions, including substance use. Maternal death rates increased during the COVID-19 pandemic and racial disparities widened for Black women. Black, AIAN, and NHPI women also have higher shares of preterm births, low birthweight births, or births for which they received late or no prenatal care compared to White women. Infants born to Black, AIAN, and NHOPI people have markedly higher mortality rates than those born to White women.

Pregnancy-Related Mortality (per 100,000 live births) by Race/Ethnicity, 2021

The disparities in maternal and infant health are symptoms of broader underlying social and economic inequities that are rooted in racism and discrimination. Differences in health insurance coverage and access to care play a role, but notably, disparities in maternal and infant health persist even when controlling for certain underlying social and economic factors, such as education and income, pointing to the roles racism and discrimination play in driving disparities. Moreover, with the overturning of Roe v. Wade and the numerous states that have enacted abortion bans across the nation, increased barriers to abortion for people of color may widen the already existing large disparities in maternal and infant health.

There have been efforts at the policy level and in clinical circles to improve maternal health and address disparities. At the state and local levels, multidisciplinary maternal mortality review committees and perinatal quality collaboratives have focused on data collection and reviewing the causes behind pregnancy-related deaths in their communities to try to prevent deaths in the future.

Fertility Assistance

Many people require fertility assistance to have children. These services include diagnostic services, treatment services, and fertility preservation. People seek fertility assistance for several reasons, such as if they or their partner has infertility, or because they are in a same-sex relationship or are single and desire children. Both female and male factors contribute to infertility, including problems with ovulation (when the ovary releases an egg), structural problems with the uterus or fallopian tubes, problems with sperm quality or motility, and hormonal factors. About 25% of the time, infertility is caused by more than one factor, and in about 10% of cases, infertility is unexplained. Infertility estimates, however, do not account for LGBTQ+ or single individuals who may also need fertility assistance for family building. Thus, there are varied reasons that may prompt individuals to seek fertility care.

Despite a need for fertility services, fertility care in the U.S. is inaccessible to many due to the cost. Fertility treatments are expensive and often are not covered by insurance. While some private insurance plans cover diagnostic services, there is very little coverage for costly treatment services such as intrauterine insemination, in vitro fertilization, and cryopreservation.

Most people who use fertility services must pay out of pocket, with costs often reaching thousands of dollars depending on the services received. This means that in the absence of insurance coverage, fertility care is out of reach for many people. Few states require private insurance plans to cover fertility assistance services, but these only apply to a subset of insurance plans and beneficiaries. Additionally, even fewer states have any fertility coverage requirement under Medicaid, the health coverage program for people with low incomes. The Trump Administration has issued an executive order requesting policy recommendations to protect access and reduce the costs for IVF, but Congressional action is required to meaningfully expand options to cover IVF services for the vast majority of people.

Abortion

Nearly 1 in 4 women in the U.S. have an abortion in their lifetime. Starting with the 1973 landmark Supreme Court ruling in Roe v. Wade, women in the U.S. had the right to abortion up until the point of viability, regardless of where they lived. On June 24, 2022, the Supreme Court issued a ruling in Dobbs v. Jackson Women’s Health Organization that overturned the constitutional right to abortion as well as the federal standards of abortion access, established by prior decisions in the cases Roe v. Wade and Planned Parenthood v. Casey. The Dobbs decision allows states to set policies regarding the legality of abortions and establish gestational limits. Access to and availability of abortions vary widely between states, with large swaths of the country banning or restricting almost all abortions, with few exceptions, and some states enshrining and protecting abortion rights (Figure 10).

Map of the United States showing the status of abortion bans as of May 7, 2025

Abortion banned in 12 states: Alabama, Arkansas, Idaho, Indiana, Kentucky, Louisiana, Mississippi, Oklahoma, South Dakota, Tennessee, Texas, West Virginia

Gestational limit between 6 and 12 weeks LMP in effect in 6 states: Florida (6 weeks), Georgia (6 weeks), Iowa (6 weeks), Nebraska (12 weeks), North Carolina (12 weeks), South Carolina (6 weeks).

Gestational limit between 15 and 22 weeks LMP in effect in 4 states: Iowa, Kansas, Ohio, and Utah

Gestational limit at or between viability (19 states): California, Connecticut, Delaware, Hawaii, Illinois, Maine, Massachusetts, Missouri, Montana, Nevada, New Hampshire, New York, North Dakota, Pennsylvania, Rhode Island, Vermont, Virginia, Washington, Wyoming

No gestational limit (9 states  & DC): Alaska, Colorado, DC, Maryland, Michigan, Minnesota, New Jersey, New Mexico, Oregon, Vermont

There are different types of abortion methods, broadly divided into procedures such as a dilation and evacuation (D&E) or dilation and curettage (D&C) and medication, which typically involves two pills – mifepristone and misoprostol. The Guttmacher Institute estimates that approximately two-thirds (63%) of all abortions are medication abortion, which can be provided by a clinician in person or by telehealth when the pills are mailed or dispensed at a retail pharmacy. Telehealth abortion care has grown in recent years, and now account for one in four abortions in the U.S.

Decades of research have shown that abortion is a very safe medical service. Still, despite its strong safety profile, abortion is the most highly regulated medical service in the country and is now banned or restricted to early gestational stages in many states. In addition to bans on abortion altogether, many states impose other limitations on abortion that are not medically indicated, including waiting periods, ultrasound requirements, and parental notification and consent requirements. These restrictions typically delay receipt of services and can increase costs associated with abortion care. As use of medication abortion has risen, some have tried to cast false doubt about the safety of the medications, despite the extensive body of research on the drug’s safety. There are multiple efforts to restrict use of the drug nationally, and two states have classified mifepristone as a controlled substance to limit its availability.

Obtaining an abortion can be costly, with median costs exceeding $500 in out-of-pocket expenses for patients who self-pay. On average, the costs are higher for abortions in the second trimester than in the first trimester. People may have to travel if abortions are prohibited or not available in their area, adding costs related to travel and lodging. Given abortion bans and Hyde Amendment restrictions on payment for abortions under Medicaid and state restrictions on insurance coverage of abortion services, many people pay for abortion services out of pocket. Some people are able to receive assistance from local abortion funds if they need financial support to obtain abortion services, particularly if they have to travel out of state or have low incomes and cannot afford the costs of the abortion. For some, however, the costs of abortion services and travel will put the service out of reach and force them to have a birth that is not desired or is a risk to their health or life.

Insurance coverage for abortion services is heavily restricted in some state-regulated private insurance plans and public programs, like Medicaid and Medicare. Private insurance covers most women of reproductive age, and states can choose whether abortion coverage is included or excluded in private plans that are not self-insured. Prior to the Dobbs ruling, about half of the states had enacted private plan restrictions and banned abortion coverage from ACA Marketplace plans. Since the Dobbs ruling, some of these states have also banned the provision of abortion services altogether. However, 12 states have enacted laws that require private plans to cover abortion, typically without cost-sharing.

The Hyde Amendment has banned the use of federal funds for abortion unless the pregnancy is a result of rape, incest, or it endangers the woman’s life. States may use non-federal state-only funds to pay for abortions under other circumstances for women covered by Medicaid, which 20 states currently do. However, more than half (56%) of women covered by Medicaid live in states where they have no coverage for abortion, unless they qualify for an exception.

The impact of the Dobbs decision goes far beyond abortion care. It has also affected the provision of related health care services, including management of miscarriages and pregnancy-related emergencies, treatments for cancer and other chronic illnesses, contraceptive options, and much more. Women with low incomes, women of color, sexual/gender minorities, and other pregnant people have been disproportionately affected by the sweeping impacts of this ruling, as they are less likely to have the resources to travel potentially long distances to seek care.

Since the Dobbs ruling, there has been a constant stream of legal challenges, with a plethora of cases that seek to challenge abortion bans as well as block access to abortion medication or services. The Supreme Court has considered two abortion related cases—one case involving the FDA’s approved conditions for using and dispensing mifepristone, one of the drugs used for medication abortion, as well as a case about potential conflict between state-level abortion bans and Emergency Medical Treatment and Labor Act (EMTALA), the federal law that requires hospitals to provide care to stabilize patients experiencing medical emergencies, including emergency abortions that must be performed to save the life or preserve the health of the pregnant patient. Several other cases about abortion access are pending in lower courts.

Paradoxically, the most recent data show that the abortion volume in the U.S. slightly increased overall in the two years following the Dobbs ruling (Figure 11). In 2024, the national abortion volume averaged 95,200 abortions per month, higher than the monthly averages in 2023 and before the Dobbs decision. This overall increase can be largely attributed to broader availability of lower cost medication abortions through telehealth, virtual clinics, brick and mortar clinics, and shield laws, where clinicians in legal states mail pills to individuals residing in states with bans and restrictions. Additionally, in several states without bans, there has been increased interstate travel for abortion access, expanded capacity to see patients, increased measures to protect abortion rights and improve coverage of abortion care.

However, the small upswing nationally obscures the massive declines in abortion access to in-state providers in states with bans and restrictions as well as the hardships that many pregnant people experience in accessing abortion care. Additionally, there are month-to-month variations in all states, and changes in policy can cause larger shifts. For example, in May 2024 Florida implemented a ban on abortions after six weeks of gestation (previously permitted up to 15 weeks), and subsequently there was a noticeable decline in abortions in the state and nationally.

While the Overall Number of Abortions in the U.S. Increased in the Two Years After Dobbs, There is Great Variation Between States That Permit and Ban Abortion (Line chart)

Contraception

Contraceptive care is an important component of overall health care for many women and people capable of becoming pregnant. Federal and state policies shape access to and the availability of contraceptive care, but factors such as provider characteristics, as well as individual preferences and experiences also impact contraceptive choices and use. For most people, private insurance coverage and Medicaid greatly reduce or eliminate financial barriers to contraceptive care. However, access is still limited in many parts of the U.S. with more than 19 million women living in contraceptive deserts where they may not have access to a health center offering the full range of contraceptive methods. There have been more efforts to broaden contraceptive availability outside of traditional clinical settings, including through commercial apps that use telehealth platforms, state efforts to allow pharmacists to prescribe birth control, and, most recently, over-the-counter (OTC) access to contraceptives without a traditional prescription.

The importance and impact of contraceptives in women’s lives are unquestionable. The 2024 KFF Women’s Health Survey highlighted that the majority of women ages 18 to 49 (82%) have used contraception in the past 12 months,  most commonly oral contraceptives and male condoms (Figure 12). The types of contraception women use shift over the course of their reproductive years. Forty-four percent of women ages 18 to 25 report having used oral contraceptives in the past 12 months compared to 19% of women ages 36 to 49. Conversely, higher shares of older women say they have had a sterilization procedure compared to younger women.

Oral Contraceptives and Male Condoms Are the Most Common Contraceptive Methods Used By Women of Reproductive Age (Bar Chart)

The ACA requires that most private plans cover contraceptive services for females without cost-sharing – this includes patient education and counseling and FDA-approved methods of contraception with a prescription. This provision has dramatically reduced cost-sharing for contraception among females with private insurance plans, though some privately insured females who are eligible for no-cost coverage are still paying some of the cost of their contraceptives (Figure 13). Reasons include someone using a brand-name contraceptive that is not in the plan’s formulary or consumers unaware of or not offered a generic alternative.

Decline in Out of Pocket Spending on Contraception Following Passage of ACA's Contraceptive Coverage Requirement (Line chart)

Despite its far-reaching impact, the ACA’s requirement for contraceptive coverage has been challenged in the courts on multiple occasions, with three cases reaching the Supreme Court. The earlier cases, Burwell v. Hobby Lobby (2014) and Zubik v. Burwell (2016), challenged the Obama Administration's regulations implementing the contraceptive coverage requirement, contending that the requirement violated some employers’ religious rights. The most recent cases, Little Sisters of the Poor v. Pennsylvania (2020) and Trump v. Pennsylvania (2020), involved regulations issued by the Trump Administration, which currently exempt employers with religious objections from providing contraceptive coverage to their employees.

For people with lower incomes, the Medicaid program is the primary funding source for contraceptives. The federal Medicaid statute establishes minimum standards, and, for decades, has classified family planning as a mandatory benefit category that all state programs must cover. States may not charge any out-of-pocket costs for family planning services and must allow beneficiaries to see any Medicaid provider within their state for family planning care. Many states also have programs that provide Medicaid coverage just for family planning services to people who have lower incomes but do not qualify for full Medicaid benefits.

Additionally, the federal Title X family planning program, administered by the HHS Office of Population Affairs (OPA), is the only federal program specifically dedicated to supporting the delivery of family planning care for individuals who are uninsured and have lower incomes. The program provides funding to more than 4,000 health clinics, public health departments, and nonprofit agencies across the country to deliver contraceptives and other family planning services to individuals with low incomes. Title X-funded providers must follow the program’s requirements, which include offering a broad range of family planning methods for low or no cost and ensuring confidentiality for adolescents. Federal rules also require that participating clinics offer their patients non-directive pregnancy option counseling that includes abortion, adoption, and prenatal referral for those who seek those services. Over the last decade, there have been major changes to the Title X program based on shifting administrations’ priorities. During the first Trump Administration, the regulations were revised to disqualify clinics that had co-located abortion services and provided abortion referrals. Over 1,000 clinics were no longer eligible for Title X funds. The Biden Administration reversed the Trump Administration regulations and funding was restored to many of these clinics. The second Trump administration has been withholding funds from some of the program’s grantees, including all 9 Planned Parenthood grantees. Hundreds of Title X Clinics are affected, and some have reported that they are closing as a result . In addition, the President’s proposed budget calls for the elimination of the Title X program.  

While there have been numerous over-the-counter contraceptive methods available (e.g. condoms, spermicides), in July 2023, the Food and Drug Administration (FDA) approved the first over-the-counter daily oral contraceptive pill, known as Opill. FDA’s approval of Opill makes it the most effective form of contraception available OTC intended for regular use. Private insurers and Medicaid generally require a prescription to cover OTC products, so even though Opill and other OTC products are available without needing a prescription from a clinician, coverage without a prescription will be limited without federal or state action.

Mental Health

Mental health has emerged as a rapidly growing concern in recent years, with 90% of Americans saying there is a mental health crisis in a 2023 KFF-CNN poll. Women experience several mental health conditions such as anxiety, depression, and eating disorders more frequently than men, and some also experience mental health disorders that are unique to women, such as perinatal depression (including prenatal and postpartum depression) and premenstrual dysphoric disorders that may occur when hormone levels change.

A KFF survey found that in 2024, a higher share of women (28%) than men (23%) describe their mental health as fair or poor (data not shown). Higher rates of women 18 to 25 (36%), those with incomes below 200% of the FPL (38%), those who identify as LGBT+ (45%), and those who identify as having a mental health-related disability (73%) report fair or poor emotional wellbeing. Roughly three in the ten women (29%) say they received mental health services from a mental health professional, however many experience challenges while trying to find care. Among women who received mental health care in the past 12 months, more than half (55%) say they experienced a barrier during their care seeking journey, including trouble finding a provider that was accepting new patients (25%), trouble finding a provider that accepted their  (21%), and trouble scheduling an appointment in a reasonable amount of time (24%).

Cost is a commonly reported barrier to mental health care. More than one in ten women 18 to 64 (13%) say they did not get mental health care or could not continue to afford the mental health care they were receiving because of cost (Figure 14). Insurance networks can be very narrow for mental health care, and a significant portion of mental health clinicians do not participate in insurance networks. These findings on cost barriers underscore the ongoing challenges with affordable mental health care, especially among women who are uninsured, but even for those with coverage.

Cost Of Mental Health Services Is A Barrier to Care Especially For Uninsured Women, But Also For Those With Insurance (Column Chart)

The ongoing opioid epidemic is a commonly cited stressor that has exacerbated long-standing mental health issues and prompted growing demand for mental health services in the past several years. Women face unique gender and sex-related differences when it comes to substance use, including greater physical, psychological, and social harms associated with drug use. Use of certain substances in women has been linked to increased rates of depression and anxiety disorders. Studies have also shown that women who use substances are at risk for issues related to pregnancy, fertility, breastfeeding, menstrual cycle, and more. All of these factors also shape the availability of treatment and services accessible to women.

Intimate Partner Violence Against Women

Intimate partner violence (IPV), defined as sexual violence, stalking, physical violence, and psychological aggression perpetrated by a current or former intimate partner, affects nearly a third of all Americans at some point in their lives. Although IPV affects men and women of all ages, women experience IPV at higher rates. Rates are higher among some groups of women, particularly those who are young, Black, American Indian or Alaska Native, and LGBTQ. People who experience IPV are more likely to experience a range of health problems such as chronic pain, cardiovascular problems, and neurological problems. Both the CDC and U.S. Preventive Services Task Force (USPSTF) have identified IPV as a significant public health issue in the U.S.

It is difficult to quantify the number of people who experience IPV, as many cases are not reported. Some studies have estimated 6.5 million women in the U.S. experience sexual violence, physical violence, or stalking by an intimate partner in a single year. According to the 2024 KFF Women’s Health Survey, one in five women report experiencing some form of IPV in the past five years (19%), including instances where a current or former partner made them fear for their safety (11%), tried to control most of all of their daily activities (11%), physically hurt them (9%), or forced them into any type of unwanted sexual activity (9%) (Figure 15).

One in Five Women ages 18 to 64 Report Experiencing Some Form of Intimate Partner Violence (IPV) in Past Five Years (Bar Chart)

Several federal programs and laws fund health care services and supports to survivors of IPV. The Violence Against Women Act (VAWA) has a broad scope, covering domestic violence, sexual harassment, stalking, and sexual assault. VAWA provides grants to states, local governments, and other organizations to establish their own violence-related programs and protocols. While some of the focus of VAWA and other public policies is prosecution of those who commit violence, provisions in VAWA also address health care coverage and costs for people who have experienced IPV.

It is well recognized that the health care system can serve as a site of IPV screening and support, and some professional medical organizations recommend that clinicians screen women for IPV. Under the ACA, IPV screening is considered a preventive service as screening is recommended by the USPSTF and Health Resources and Services Administration (HRSA) preventive services for women. When health care providers routinely screen patients for IPV, it helps identify cases and connect survivors to resources and supports. However, this can be challenging as a KFF survey of OBGYNs found that many clinicians say they do not have sufficient resources within their practices to provide follow-up services when cases of IPV are identified. Connections to community-based services are particularly important for clinicians to be able to care for patients who disclose IPV.

Future Outlook

Copy link to Future Outlook

Women’s health has become one of the most politicized issues in society and health care. The overturning of Roe v. Wade in 2022 marked a seismic change in an important aspect of women’s health care that has implications for all pregnancy-related care and women’s economic future and well-being. The high and rising rates of maternal mortality and morbidity in the U.S. and the persistent gaps in mortality rates experienced by women of color highlight the need to address the roles that poverty, racism, and discrimination play in women’s health.

The Trump Administration has proposed major changes that could affect many recent gains in women’s health care. Within the first few months of taking office, the Administration has sought to define sex as “an individual’s immutable biological classification as either male or female,” which is not supported by science, proposed to eliminate the Office of Population Affairs (OPA), and raised doubts about the safety of mifepristone without scientific basis, to name a few. Significant cuts to several HHS agencies, including HRSA, CDC, FDA, and NIH, have reduced support for women’s health programs and research across the country, with more likely to come. The Administration opposes federal programs related to racial equity, which is integrally connected with most women’s health issues such as maternal health. In addition, the federal budget reconciliation law that was enacted in 2025 made major cuts to the Medicaid program and the ACA, which will affect access to affordable coverage and care for women and families with low incomes. Over the next several years, these cuts in federal spending are projected to lead to a steep rise in people who are uninsured and reduced funding for states and health care providers, including those that care for women with lower incomes. At the same time, the Administration is calling for an increase in births while cutting programs that support families, such as food stamps and HeadStart. While much of the focus in the years will be on the effects of these cuts to federal health spending and programs, some of the key challenges that remain to be addressed in women’s health include:

  • How to address and eliminate the persistent inequities in health coverage and outcomes experienced by women of color?
  • How to build a delivery system and develop coverage policies that is responsive to the reproductive and sexual health needs of women and other gender minorities to promote optimal health outcomes?
  • How to maintain a strong safety-net that offers high quality sexual and reproductive health services, with rising health care costs, a potential increase in uninsured rates, and a decrease in public funds?
  • How to shape policies that protect women with low incomes from experiencing financial barriers to care
  • Identifying and implementing policies that improve maternal health outcomes and also eliminate the structural and systemic barriers to care
  • Providing access to comprehensive care to pregnant people who live in areas where abortion is unavailable due to state-level bans and restrictions
  • How to provide care to women dealing with issues that are heavily stigmatized and marginalized, such as intimate partner violence and mental health challenges.

Resources

Copy link to Resources

Citation

Copy link to Citation

Ranji, U., Diep, K., Gomez, I., Sobel, L., & Salganicoff, A., Health Policy Issues in Women's Health. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-health-policy-issues-in-womens-health/ (date accessed).

Race, Inequality, and Health

Table of Contents

Introduction

Copy link to Introduction

Health and health care disparities refer to preventable differences in health and health care among groups that stem from broader social and economic factors. Despite the recognition of disparities for decades and overall improvements in population health over time, many disparities persist, and in some cases, have widened over time. Disparities limit the overall health of the nation and result in unnecessary costs. This chapter provides an overview of what health and health care disparities are, the factors that drive them, the status of racial and ethnic health and health care disparities today, how recent federal actions may impact disparities, and future considerations. The information and data included in this chapter are current as of July 2025.

In the wake of the COVID-19 pandemic and racial reckoning following the murders of George Floyd and others, the federal government as well as many states and private entities increased efforts focused on addressing health disparities. Since taking office, the Trump administration has taken a range of actions to eliminate federal diversity and disparities-related initiatives, restructured and eliminated federal staff and offices that played key roles in identifying and addressing disparities, and implemented policies focused on restricting immigration and increasing interior enforcement to support mass deportation of immigrants. Moreover, the 2025 federal budget reconciliation law makes large cutbacks to federal spending for Medicaid and the Affordable Care Act’s (ACA’s) provisions. These actions will likely lead to widening disparities in health and health care going forward.

What are Health and Health Care Disparities?

Copy link to What are Health and Health Care Disparities?

Health and health care disparities refer to preventable differences in health and health care among groups that stem from broader social and economic factors. There are multiple definitions of health disparities. The Centers for Disease Control and Prevention (CDC) defines health disparities as “preventable differences that populations experience in the burden of disease, injury, violence, or opportunities.” A health care disparity typically refers to differences between groups in health insurance coverage, affordability, access to and use of care, and quality of care. The terms “health inequality” and “inequity” also are used to describe differences that stem from systemic and unjust or inequitable social and economic policies. Racism, which the CDC previously defined as a system that includes structural, institutional, interpersonal, and internalized racism that assigns value and determine opportunities based on the way people look or the color of their skin, results in conditions that unfairly advantage some and disadvantage others. Racism and discrimination at all levels, intentional or not, contribute to differences in experiences across many aspects of everyday life as well as in health care settings, which can negatively impact people’s health and well-being.

Reflecting the intersectional nature of people’s identities, some individuals experience disparities across multiple dimensions beyond race and ethnicity such as citizenship, sexual orientation and gender identity, and disability status.  Disparities also occur within subgroups of broader racial and ethnic groups, such as gender, ethnic identity, immigration status, and English proficiency. For example, a KFF survey shows that Black women report more pervasive negative experiences in health care settings compared to other groups. These groups are not mutually exclusive and often intersect in meaningful ways.  The Healthcare Research and Quality Act of 1999, which established an Office of Priority Populations within the Agency for Healthcare Research and Quality (AHRQ) identifies designated priority populations, including “low-income populations, racial/ethnic minorities, maternal health, women, children/adolescents, elderly, and individuals with special health care needs.” The National Institute on Minority Health and Health Disparities, established under the Minority Health and Health Disparities Research and Education Act also has designated populations with health disparities, including “racial and/or ethnic minority populations, low socioeconomic status, underserved rural populations, people with disabilities, and sexual minority groups.”

Health equity generally refers to individuals achieving their highest level of health through the elimination of disparities in health and health care. The CDC describes health equity as when everyone has a fair and just opportunity to be as healthy as possible. The World Health Organization (WHO) states that “health equity is achieved when everyone can attain their full potential for health and well-being.” The WHO defines equity as the absence of unfair and avoidable differences among groups, regardless of their identity, where they live, and other social and economic factors. The terms health equity and equality both refer to efforts to achieve better health outcomes and access to health care services for all groups. While health equality refers to providing all people with the same resources and opportunities, it does not account for people’s different underlying needs or circumstances that may affect their ability to achieve optimal health outcomes and health care access.

What Factors Drive Racial and Ethnic Health Disparities?

Copy link to What Factors Drive Racial and Ethnic Health Disparities?

The U.S. has a long history of policies and events that have resulted in stark differences in access to resources, opportunities, and power that contribute to racial and ethnic disparities in health today. Dating back to slavery and colonization of the Americas, people of color have been subject to abuse and mistreatment, including medical exploitation and experimentation, family separation, and efforts to eliminate cultural practices and languages. Historical discriminatory policies, such as redlining, have lasting effects today, leading to residential segregation of Black and Hispanic people into urban neighborhoods with more limited resources and increased health risks, including climate-related risks. Within medicine, disproven beliefs about biological differences by race persist today and have led to race permeating clinical decision making and treatment in multiple ways, including through providers’ attitudes and implicit biases, disease stereotyping and clinical nomenclature, and its use in clinical algorithms, tools, and treatment guidelines. Similarly, historical anti-immigrant policies have excluded and discriminated against certain groups, contributing to “othering” and “perpetual foreigner” stereotypes, particularly among Asian immigrants, with a resurgence in anti-Asian rhetoric amid the COVID-19 pandemic. Policies, such as the 1996 Welfare Reform Law, have restricted access to public assistance programs, including health coverage, contributing to persistent disparities in health coverage and care for immigrants today, who are disproportionately Hispanic or Asian.

Underlying inequities in social and economic factors that reflect historical and contemporary policies drive racial and ethnic disparities in health (Figure 1). Though health care is essential to health, studies suggest that social and economic factors, often referred to as  social determinants of health, are the primary drivers of health outcomes. These include factors such as access to housing, food, and economic and educational opportunities. Hispanic, Black, AIAN, and NHPI people fare worse compared to White people across many social and economic factors. Experiences for Asian people are mixed, although some subgroups of Asian people fare worse compared to White people. Asian immigrants face certain additional challenges.

Experiences with unfair treatment and discrimination negatively impact health and well-being. Despite growing calls to address racism in the wake of the COVID-19 pandemic and the accompanying racial reckoning, many adults continue to experience unfair treatment and discrimination in their daily lives and in health care settings. A 2023 KFF survey finds that at least half of AIAN (58%), Black (54%), Hispanic adults (50%), and about 4 in 10 Asian adults (42%) say they experienced at least one type of discrimination in daily life in the past year. These experiences include receiving poorer service than others at restaurants or stores; people acting as if they are afraid of them or as if they aren’t smart; being threatened or harassed; or being criticized for speaking a language other than English. Consistent with other research, which shows that racism has negative effects on mental health and results in certain negative physical health outcomes, among those with discrimination experiences, 4 in 10 (40%) say they “always” or “often” felt anxious in the past year, compared to 14% of adults who rarely or never experience such discrimination (Figure 2). Similarly, those with experiences of discrimination in their daily life are more than three times as likely as others to say they always or often felt lonely (26% vs. 7%) or depressed (25% vs. 7%) in the past year.

Adults Who Experience Discrimination Are More Likely Than Those Who Do Not To Report Feeling Anxious, Lonely, Or Depressed

Racism and discrimination also negatively affect people’s health care experiences. KFF survey data also show that Black, Hispanic, AIAN, and Asian adults report higher levels of unfair treatment when seeking health care than their White counterparts and are more likely to report having certain negative experiences with a health care provider because of their race and ethnicity (Figure 3). About a quarter of adults who experienced unfair treatment, a negative experience with a provider, or a language access challenge say it led to worse health, being less likely to seek care, and/or switching providers. Similarly, as of 2023, one in four (25%) immigrant adults said that they were treated unfairly by a health care provider in the U.S., including nearly four in ten (38%) Black immigrant adults.

About One In Five Black Adults And One In Ten Hispanic, Asian, And AIAN Adults Report Unfair Treatment By A Health Care Provider Due To Race Or Ethnicity

Why Is It Important to Address Disparities?

Copy link to Why Is It Important to Address Disparities?

Addressing disparities in health and health care is important not only from an equity standpoint but also for improving the nation's overall health and economic prosperity. Racial and ethnic health and health care disparities result in higher rates of illness and death across a wide range of health conditions, limiting the overall health of the nation. Research further finds that health disparities are costly, resulting in excess medical care costs and lost productivity, as well as additional economic losses due to premature deaths each year.

It is increasingly important to address health disparities as the population becomes more diverse and stark income inequalities persist (Figure 4). The population has become increasingly racially diverse, reflecting shifting immigration patterns, a growing multiracial population, as well as adjustments to how the U.S. Census Bureau measures race and ethnicity. The U.S. Census Bureau projects that people of color will account for over half (52%) of the population in 2050, with the largest growth occurring among people who identify as Asian or Hispanic. Income inequality within the U.S. has also widened over time. As of 2023, the top 10% of households in the U.S. had incomes above $216,000 compared with incomes at or below $17,100 among the lowest 10% of households.

People Of Color Are Projected To Make Up Over Half Of The U.S. Population As Of 2050

What Is the Status of Racial and Ethnic Disparities in Health Today?

Copy link to What Is the Status of Racial and Ethnic Disparities in Health Today?

Major recognition of health disparities began nearly four decades ago. In 1985, the Report of the Secretary’s Task Force on Black and Minority Health (commonly known as the Heckler Report) documented persistent health disparities that accounted for 60,000 excess deaths each year and synthesized ways to advance health equity. The Heckler Report led to the creation of the Office of Minority Health within the Department of Health and Human Services (HHS) (which was reportedly shut down by the Trump administration as part of the HHS staff restructuring and reductions) and influenced federal recognition of and investment in many aspects of health equity. In 2003, the Institute of Medicine’s Unequal Treatment: Confronting Racial and Ethnic Disparities in Health Care report was issued, which identified systemic racism as a major cause of health disparities in the United States.

Despite the recognition and documentation of disparities for decades and overall improvements in population health over time, many disparities persist, and in some cases, have widened over time .Analysis across a broad range of health measures finds that Black and AIAN people fare worse than their White counterparts across half or more of these measures. Data for Hispanic people are more mixed relative to White people, with them faring better on some measures but worse on others. In the aggregate, Asian people fare the same or better than White people on many measures of health, although this finding masks disparities among subgroups of the population. Data gaps limit the ability to examine disparities among NHPI people; where data are available, they point to disparities, particularly for certain subgroups of this population. Overall, Black, Hispanic, and AIAN people fare worse compared to White people across many measures of health outcomes including:

  • AIAN and Black people had a shorter life expectancy at birth compared to White people based on provisional data from 2022. Life expectancy for Black people was about five years shorter than White people (72.8 vs. 77.5), and nearly ten years shorter for AIAN people (67.9).
  • AIAN, Hispanic, and Black people experienced larger declines in life expectancy than White people between 2019 and 2021, largely reflecting an increase in excess deaths due to COVID-19.
  • NHPI people had the highest age adjusted mortality rates for diabetes among all racial and ethnic groups at 49.6 per 100,000 deaths. The age-adjusted mortality rates for diabetes for AIAN (41.5 per 100,000) and Black people (39.1 per 100,000) were about twice as high as the rate for White people (19.8 per 100,000); Hispanic people (26.5 per 100,000) also had a higher diabetes death rate compared to White people in 2023. Although Black people did not have higher cancer incidence rates than White people overall and across most types of cancer, they had the highest overall cancer-related mortality rate as of 2022. Black people (165 per 100,000 deaths) were more likely to die from cancer than White people (148.4 per 100,000), and NHPI people had a slightly lower overall cancer-related mortality rate (141.4) to White people in 2022.
  • Black infants were more than two times as likely to die as White infants (10.9 vs. 4.5 per 1,000 live births) as of 2023. AIAN infants (9.1 per 1,000) were roughly twice as likely to die as White infants (Figure 5). Hispanic infants (4.9 per 1,000) also had a slightly higher mortality rate than White infants in 2023.
  • AIAN (118.7 per 100,000), NHPI (111.7 per 100,000), and Black (69.3 per 100,000) women also had the highest rates of pregnancy-related mortality in 2021
Black, AIAN, and NHPI People Have Higher Infant Mortality Rates Compared To Other Groups  

There are also ongoing racial and ethnic disparities in health coverage and access to care.  Despite large gains in coverage across groups since the ACA coverage expansions were implemented in 2014, as of 2022, nonelderly AIAN, Hispanic, Black, and NHPI people were more likely to be uninsured compared to their White counterparts (Figure 6). There are also large coverage disparities by immigration status, with a 2023 KFF/LA Times Survey of Immigrants showing that about one in five (18%) lawfully present immigrant adults and half (50%) of likely undocumented immigrant adults reported being uninsured as compared to less than one in ten citizens. In addition, Hispanic, Black, Asian, AIAN, and NHPI adults are more likely than White adults to report not having a personal health care provider, and Hispanic, Black, AIAN, and NHPI adults are more likely than White adults to report not seeing a doctor in the past 12 months because of cost.

Despite Large Gains In Coverage, Racial And Ethnic Disparities Remain

How Could Recent Federal Actions Impact Disparities?

Copy link to How Could Recent Federal Actions Impact Disparities?

In the wake of the COVID-19 pandemic and racial reckoning following the murders of George Floyd and others, the federal government as well as many states and private entities increased efforts focused on addressing health disparities. This increased focus led to the development of programs and initiatives focused on mitigating disparities, including efforts to address disparities in maternal and infant health, cancer, and chronic disease, as well as other efforts, such as increasing diversity in clinical trials for development of new drugs and devices. Research efforts also increased to understand disparities, the factors driving them, and effective interventions to mitigate them.

The Biden administration issued a series of executive orders and other efforts to advance health equity.  These included orders that outlined equity as a priority for the federal government, equity as a central part of the pandemic response and recovery efforts, and also directed federal agencies to develop Equity Action Plans. HHS’ equity action plan outlined a series of strategies that included efforts to improve access and address barriers to quality and affordable health care; prioritize behavioral health for underserved populations; and improve maternal health outcomes for rural, Tribal, and underserved racial and ethnic groups. HHS also enacted its climate action plan, including establishing the Office of Climate Change and Health Equity to address the impacts of climate change on health outcomes and health equity.  The administration released a Blueprint for Addressing the Maternal Health Crisis, a whole government approach to combatting maternal mortality and morbidity with a focus on reducing disparities in maternal health outcomes and improving overall pregnancy, birth, and postpartum outcomes. Federal efforts were also made to increase the availability of disaggregated data for smaller population groups, including AIAN and NHPI people, to understand and address the health and heath care disparities they face. During his term, President Biden reversed public charge regulations from the Trump administration’s first term to reduce fears about participating in programs, including Medicaid and the Children’s Health Insurance Program.

As one of his first actions in office, President Trump signed executive orders revoking federal diversity, equity, inclusion, and accessibility (DEIA) related programs and actions in the federal government and among federal contractors and grantees.  In implementing President Trump’s executive orders, the administration has taken significantly broader actions beyond eliminating DEI programs to eliminate priorities, actions, information, data, and funding related to concepts of diversity or disparities among federal agencies as well as federal contractors and grantees.The Office of Personnel Management directed agencies and departments to take down all outward facing media that “inculcate or promote” “gender ideology,” as well as to remove all public facing DEI related websites and content. This resulted in the temporary shutdown of websites and removal of key health datasets. While some web pages and datasets began returning in several days, they included a warning message that they were being modified to comply with President Trump’s executive orders and some materials, such as codebooks and questionnaires, did not immediately return. The administration also directed departments and agencies to pause grants provided to federal contractors to identify and review programs and activities for consistency with the President’s policies. Reports indicate that the administration flagged over 100 words that federal agencies should limit or avoid to comply with the President’s policies, including disparities, diversity, equity, and race; that the CDC ordered the withdrawal of papers pending publication to ensure language compliance; and that research grants were terminated to comply with new restrictions. As part of efforts to eliminate diversity and disparities related initiatives the administration also eliminated environmental justice actions and programs

The administration also eliminated about 10,000 employees from HHS, including many of those focused on addressing disparities as part of a restructuring effort. The HHS Office of Minority Health, CDC’s Office of Health Equity, the Office of Women’s Health, and the Office for Civil Rights are among the offices facing partial or complete cuts. The impact of these cuts is compounded by the loss of population-specific initiatives and offices. The administration’s proposed budget cuts to the Indian Health Services (IHS) and HHS include $900 million in cuts to the IHS budget and eliminating advanced appropriations.  In addition to eliminating staff directly working on disparities, other cuts were made that will have important implications for disparities. The restructuring cut jobs from the CDC’s National Center for Chronic Disease Prevention and Health Promotion, which has resulted in the termination of programs focused on diabetes, obesity, dementia, and kidney disease, which disproportionately affect people of color. The HHS restructuring has also impacted federal maternal and infant health programs, including layoffs of most staff at the CDC’s Division of Reproductive Health, which serves to provide data, research, and assistance to states “on issues related to reproductive health, maternal health, and infant health.” These staff cuts are accompanied by the suspension of the Pregnancy Risk Assessment Monitoring System, which has documented disparities in maternal mortality and morbidity for 38 years.

The actions to eliminate diversity and disparities related initiatives will likely lead to widening disparities, reversing recent efforts to advance health equity. Elimination of focused efforts to address health disparities will potentially further exacerbate disparities, contributing to worsening overall health and unnecessary health care costs. Focused plans and initiatives to mitigate health disparities seek to address the underlying inequities that drive disparities and meet the needs and preferences of diverse populations. In the absence of focused efforts, disparities will likely widen because the underlying inequities that contribute to them persist. Additionally, the elimination of information, data, and research will inhibit the ability to identify disparities and understand the factors driving them. Data are essential for identifying where disparities exist, directing efforts and resources to address disparities as they are identified, measuring progress toward achieving greater equity, and establishing accountability for achieving progress. Without adequate data and research, disparities may remain unseen and unaddressed.

The Trump administration has also made immigration policy changes focused on restricting entry at the border and increasing interior enforcement efforts to support mass deportation, which may contribute to widening disparities among immigrant families. Research suggests that these policies negatively affect the health and well-being of immigrant families, including citizen children living in these families. KFF survey data from 2025 show that immigrants’ worries about detention or deportation have risen sharply since 2023, even among lawfully present immigrants and naturalized citizens, and many say these worries are affecting their health. Moreover, accompanying KFF focus groups  found that immigration policies and actions undertaken by the Trump administration have led to increased fears, uncertainty, and financial hardships among immigrant families across immigration statuses that have had negative effects on their daily lives, health, and well-being, including negative mental health impacts on them and their children. Efforts to restrict immigration not only impact the health and well-being of immigrant families, but can also negatively impact the U.S. economy and workforce, given the role immigrants play, particularly in certain industries such as health care, construction, and agriculture.

Under the recently passed budget reconciliation law there are large cuts to federal spending for Medicaid and the ACA, which will likely lead to widening racial and ethnic disparities in health coverage and, in turn, exacerbate disparities in access to care. Medicaid is a major source of coverage for people of color, helping to fill gaps in employer sponsored coverage, particularly for children (Figure 7). The ACA’s coverage expansions through Medicaid and the Marketplaces contributed to large gains in health coverage across racial and ethnic groups and reduced racial disparities in coverage. The law includes substantial cuts to federal Medicaid spending and changes to the ACA, which the Congressional Budget Office projects will increase the number of uninsured by about 10 million by 2034. The law includes provisions that eliminate eligibility for Medicaid, subsidized ACA Marketplace, and Medicare coverage for many lawfully present immigrants. In addition to reductions in the legislation, the scheduled expiration of tax credits for Marketplace coverage in 2025 and recent Trump administration regulatory changes that make it harder to sign up for ACA coverage are expected to further increase the growth in the uninsured by millions.  Coverage losses, particularly in Medicaid, would widen racial and ethnic disparities in coverage given that larger shares of people of color are covered by the program. In turn, widening disparities in coverage would likely contribute to gaps in access to care and ultimately health outcomes.

Interactive Datawrapper Embed

Future Outlook

Copy link to Future Outlook

Looking to the future, racial and ethnic disparities in health and health care remain a persistent problem, particularly as longstanding efforts to recognize and address them are being dismantled. These disparities are rooted in the ongoing impacts of racism and discrimination, which contribute to structural inequities in access to resources, opportunities, and health care as well as bias within health systems and daily life. As efforts to advance health equity face increasing challenges some key issues include:

How to mitigate bias and disparate treatment in the medical system, amid the growing use of AI and data-driven tools in health care and perpetuation of disproven beliefs about biologic differences by race.

How rollbacks to federal disparities initiatives and DEI programs will impact long term efforts to address disparities in health.

How to close racial and ethnic gaps and prevent further widening of disparities in health coverage and access to care amid efforts to cut Medicaid and other public programs.

What data and research will remain available to identify and understand disparities and develop interventions to address them.

How uneven impacts of climate change and climate-related health risks may impact disparities amid the rollbacks of federal environmental justice efforts.

Resources

Copy link to Resources

Citation

Copy link to Citation

Ndugga, N., Pillai, D., Hill, L., & Artiga, S., Race, Inequality, and Health. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-race-inequality-and-health/ (date accessed).

The Role of Public Opinion Polls in Health Policy

Table of Contents

Introduction

Copy link to Introduction

Polls and surveys are useful tools for understanding health policy issues. However, it takes time and training to understand how to interpret survey results and to decide which polls are useful and which might be misleading. The aim of this chapter is to help you learn how to be a good consumer of polls so they can be a valuable part of your toolkit for understanding the health policy environment. It begins by discussing why polls are an important tool in policy analysis and the caveats to keep in mind when interpreting them. It then discusses polling methodology and the questions you should ask to assess the quality and usefulness of a poll. The chapter ends with some real-world examples in which polling helped inform policy debates.

People sometimes ask if there is a difference between a “poll” and a “survey.” The quick answer is that every poll is a survey, but not every survey is a poll (for example, large federal surveys like the Census or surveys of hospitals or other institutions would not be called polls). For purposes of this chapter, we use the terms interchangeably.

Why Should You Pay Attention to Polls at all?

Copy link to Why Should You Pay Attention to Polls at all?

Polls have gotten a bad rap over the past few years, particularly around election times when they don’t do a perfect job predicting who the winner of a given election will be. Given this, you may wonder why you should pay attention to polls when trying to understand health policy. There are six basic reasons why it’s important for health policy scholars to understand public opinion:

1. People vote, and elections can have important consequences for health policy at the local, state, and national levels. While polls may not always be perfect predictors of election outcomes, they are one of the best ways to understand the dynamics of how voters are thinking and feeling when weighing their vote choices, not only for high-profile offices like President and Congress, but for state and local races and ballot initiatives as well.

2. Public opinion can influence policy choices, particularly for highly salient issues, like health care, that touch pretty much everyone’s lives in some way. While the average member of the public may not be equipped to understand the details of most health policy legislation, their preferences and views can put constraints on lawmakers by identifying actions that would be deemed unacceptable by large majorities of the public or their constituents.

3. Polls can also provide information about the broader environment in which health policy issues or changes are being debated. They can help you understand the salience of a given issue (i.e., how much do people care about prescription drug prices and how closely are they paying attention to debates over how to lower them?) and identify other factors that might affect the likely success of a given policy (i.e., if the country’s attention is focused on a foreign policy crisis, how will that affect the public’s reaction to a major new proposal to overhaul Medicaid?).

4. Beyond measuring opinion, surveys can also be useful for understanding how health policy is affecting people. Survey questions about people’s experiences can offer context by providing information like the share of people who are struggling to afford their health insurance. Looking at questions like these at multiple points in time can also help you understand how experiences change in the months and years following enactment of major health legislation.

5. Surveys can help amplify the voices of real people in policy debates, particularly those that are often ignored or drowned out by special interests. Polling that includes adequate sample sizes to represent the voices of marginalized and underrepresented populations, such as members of racial and ethnic minority groups, immigrants, LGBTQ individuals, people living in rural areas, and those with lower incomes, may be especially useful for understanding the impact of health policy on people.

6. In this way, methodologically sound, non-partisan, transparent surveys can serve as a counterweight to polls sponsored by special interests that are conducted in private and used to craft public messages, design campaigns, or sell products.

Caveats to Polling

Copy link to Caveats to Polling

Polls do not tell the whole story. Public opinion is just one part of the political and policymaking process. Public support for a given policy may seem clear based on a single survey question, but it can be quite malleable in the course of a public debate, and not all surveys measure this malleability. Small changes in survey question wording can sometimes lead to big changes in public support, so it’s important never to rely on a single question from a single poll to make a conclusion about what the public thinks or knows. When possible, look for multiple questions on the same topics from multiple polls conducted at various times. If the answers are consistent, you can be more confident that the conclusion is correct. Sometimes a poll finding conflicts with your best sense of political reality when all available information is considered. In those instances, there’s a good chance your “gut” is a better guide than what a given poll tells you.

There are limits to polling on complex topics like health care. When the public says they support a specific proposal for lowering health care costs, it doesn’t mean they have fully thought through the details of that proposal and its implications. Rather, it may signal how important they think it is for policymakers to address the high cost of health care. And while some polls test this by asking follow-up questions that probe the public about trade-offs to any given policy approach, some health policy topics are just too complicated to reasonably ask the average American to weigh in on in a short survey.

Public opinion can’t give you the “right” answer. While public opinion can tell you where the public stands on an issue, it cannot tell you what the right policy solution is in any given situation. For example, pollsters often ask people to rank the priority they give to different health issues before Congress. They may ask the public to rank the issues of prescription drug costs, the future of the Affordable Care Act, Medicaid expansion, the financial sustainability of Medicare, and so forth. But it turns out that real people aren’t organized like congressional committees and don’t put the issues neatly into policy buckets like pollsters do. What they are concerned about is the cost and affordability of health care, a concern that cuts across these issues. These ranking questions provide some information about what resonates most with the public, but that doesn’t mean they should be treated as a rank-ordered list for policymakers to address starting from the top down. In addition, beyond telling you what the public thinks, polls can be just as useful for pointing out what the public doesn’t understand about a given policy issue, allowing you to direct outreach and education efforts or figure out messaging that will resonate with the public if you are advocating for a policy change.

Understanding the Methods: Questions to Ask about Polls

Copy link to Understanding the Methods: Questions to Ask about Polls

The science of survey research is complicated, but there are a few simple terms you can learn and questions you can ask when you encounter polls in your schooling and daily life. These include:

Population. Who is the population that the survey is claiming to represent? Polls can be conducted with many different populations, so it is important to know how researchers define the population under study. For example, a survey of voters may be useful for your understanding of a particular health care issue’s importance in the election, but it might not be as useful for estimating how many people have had problems paying medical bills, since lower-income people (who may be the most likely to experience bill problems) are less likely to be voters and may be left out of the study entirely.

Sampling. How did researchers reach the participants for their poll, and was it a probability or non-probability sample? In a probability-based sample, all individuals in the population under study have a known chance of being included in the survey. Such samples allow researchers to provide population estimates (within a margin of sampling error) based on a small sample of responses from that population. Examples of probability-based sampling techniques include random digit dialing (RDD), address-based sampling (ABS), registration-based sampling (RBS), and probability-based online panels. Non-probability sampling, sometimes called convenience or opt-in sampling, has become increasingly common in recent years. While non-probability surveys have some advantages for some types of studies (particularly their much lower cost), research has shown that results obtained from non-probability samples generally have greater error than those obtained from probability-based methods, particularly for certain populations.

Data collection (survey mode). While there are many ways to design a survey sample, there are also many ways to collect the data, known as the survey mode. For many years, telephone surveys were considered the gold standard because they combined a probability-based sampling design with a live interviewer. Survey methodology is more complicated now, but it is still important to know whether the data was collected via telephone, online, on paper, or some other way. If phones were used, were responses collected by human interviewers or by an automatic system, sometimes known as interactive voice response (IVR) or a “robocall”? Or were responses collected via text message? Depending on the population represented, different approaches might make the most sense. For example, about 5% of adults in the U.S. are not online, and many others are less comfortable responding to survey questions on a computer or internet-connected device. While young adults may be comfortable responding to a survey via text message, many older adults still prefer to take surveys over the phone with a live interviewer. Some populations feel a greater sense of privacy when taking surveys on paper, while literacy challenges may make a phone survey more appropriate for other populations. Many researchers now combine multiple data collection modes in a single survey to make sure these different segments of the population can be represented.

Language. Was the survey conducted only in English, or were other languages offered? If the survey is attempting to represent a population with lower levels of English language proficiency, this may affect your confidence in the results.

Survey sponsor. Who conducted the survey and who paid for it? Understanding whether there is a political agenda, special interest, or business behind the poll could help you better determine the poll’s purpose as well as its credibility.

Timing. When was the survey conducted? If key events related to the survey topic occurred while the survey was in the field (e.g., an election or a major Supreme Court decision), that might have implications for your interpretation of the results.

Data quality checks. During and after data collection, what data quality checks were implemented to ensure the quality of the results? Most online surveys include special “attention check” questions designed to identify respondents who may have fabricated responses or rushed through the survey without paying attention to the questions being asked. Inclusion of these questions is a good sign that the researchers were following best practices for data collection.

Weighting. Were the results weighted to known population parameters such as age, race and ethnicity, education, and gender? Despite best efforts to draw a representative sample, all surveys are subject to what is known as “non-response bias” which results from the fact that some types of people are more likely to respond to surveys than others. Even the best sampling approaches usually fall short of reaching a representative sample, so researchers apply weighting adjustments to correct for these types of biases in the sample. When reading a survey methodology statement, it should be clear whether the data was weighted, and what source was used for the weighting targets (usually a survey from the Census or another high-quality, representative survey).

Sample size and margin of sampling error. The sample size of a survey (sometimes referred to as the N) is the number of respondents who were interviewed, and the margin of sampling error (MOSE) is a measure of uncertainty around the survey’s results, usually expressed in terms of percentage points. For example, if the survey finds 25% of respondents give a certain answer and the MOSE is plus or minus 3 percentage points, this means that if the survey was repeated 100 times with different samples, the result could be expected to be between 22%-28% in 95 of those samples. In general, a sample size of 1,000 respondents yields a MOSE of about 3 percentage points, while smaller sample sizes result in larger MOSEs and vice versa. Weighting can also affect the MOSE. When reading poll results, it is helpful to look at the N and MOSE not only for the total population surveyed, but for any key subgroups reported. This can help you better understand the level of uncertainty around a given survey estimate. The non-random nature of non-probability surveys makes it inappropriate to calculate a MOSE for these types of polls. Some researchers publish confidence estimates, sometimes called “credibility intervals,” to mimic MOSE as a measure of uncertainty, but they are not the same as a margin of sampling error. It’s also important to note that sampling error is only one source of error in any poll.

Questionnaire. Responses to survey questions can differ greatly based on how the question was phrased and what answer choices were offered, so paying attention to these details is important when evaluating a survey result. Read the question wording and ask yourself – do the answer options seem balanced? Does the question seem to be leading respondents toward a particular answer choice? If the question is on a topic that is less familiar to people, did the question explicitly offer respondents the chance to say they don’t know or are unsure how to answer? If the full questionnaire is available, it can be helpful to look at the questions that came before the question of interest, as information provided in these questions might “prime” respondents to answer in a certain way.

Transparency. There is no “gold seal” of approval for high-quality survey methods. However, in recent years, there has been an increasing focus on how transparent survey organizations are about their methods. The most transparent researchers will release a detailed methodology statement with each poll that answers the questions above, as well as the full questionnaire showing each question in the survey in the order they were asked. If you see a poll released with a one or two-sentence methodology statement and can’t find any additional information, that may indicate that the survey organization is not being transparent with its methods. The American Association for Public Opinion Research has a Transparency Initiative whose members agree to release a standard set of information about all of their surveys. Some news organizations also “vet” polls for transparency before reporting results, but many do not. This means that just because a poll or survey is reported in the news doesn’t necessarily mean it’s reliable. It’s always a good idea to hunt down the original survey report and see if you can find answers to at least some of the questions above before making judgments about the credibility of a poll.

Election polling vs. issue polling. Election polls – those designed at least in part to help predict the outcome of an election – are covered frequently in the media, and election outcomes are often used by journalists and pundits to comment on the accuracy of polling. Issue polls – those designed to understand the public’s views, experiences, and knowledge on different issues – differ from election polls in several important ways. Perhaps the most important difference is that, in addition to the methodological challenges noted above, election polls face the added challenge of predicting who will turn out to vote on election day. Most election polls include questions designed to help with this prediction, and several questions may be combined to create a “likely voter” model, but events or other factors may affect individual voter turnout in ways pollsters can’t anticipate. Election polls conducted months, weeks, or even days before the election also face the risk that voters will change their mind about how to vote between the time they answer the survey and when they fill out their actual ballot. Issue polls do not generally face these challenges, so it’s important to keep in mind that criticisms about the accuracy of election polls may not always apply to other types of polls.

Examples of the Usefulness of Polls in Understanding Health Policy

Copy link to Examples of the Usefulness of Polls in Understanding Health Policy

Example #1: Tracking the evolution of public opinion and experience through debate, passage, and implementation of the Affordable Care Act

The Affordable Care Act (ACA) is the largest health legislation enacted in the 21st century. From the time the legislation was being debated in Congress through its passage, implementation, and efforts to repeal it, the ACA has been the subject of media coverage, political debate, campaign rhetoric, and advertising. In each of those stages, polls and surveys have provided important information for understanding what was happening with the law.

Prior to passage, polls showed the public’s desire for change in health care, particularly when it came to decreasing the uninsured rate and making health care and insurance more affordable. Despite this apparent consensus on the need for change, polls also helped shed light on some of the barriers to passing legislation. For example, survey trends demonstrated how the share of the public who expected health reform legislation to leave their families worse off increased over the course of an increasingly public debate in which opponents tapped into fears about how the proposed law might change the status quo.

After the law was passed, public opinion on the ACA was sharply divided along partisan lines, with majorities of Democrats viewing the law favorably and majorities of Republicans having an unfavorable view. However, surveys also painted a more nuanced picture beyond the overall partisanship, showing that majorities of U.S. adults across partisan lines favored many of the things the ACA did, including allowing young adults to stay on their parents’ insurance until age 26, preventing health plans from charging sick people more than healthy people, and providing financial subsidies to help lower- and moderate-income adults purchase coverage. At the same time, polls showed that many adults were not aware that these provisions were part of the ACA, and that many others incorrectly believed the law did things it did not, such as creating a government-run insurance plan and allowing undocumented immigrants to receive government financial help to purchase coverage.

This combination of “the parts more popular than the whole” and incomplete public knowledge of the law provided some insight into why efforts to repeal the law were ultimately unsuccessful despite the relative unpopularity and deep partisan divisions on the law overall. When faced with the very real prospect of the popular parts of the law going away – particularly the protections for people with pre-existing health conditions – the public (and particularly Democrats and independents who had previously expressed lukewarm support) rallied to protect it. In fact, following concerted Republican efforts to repeal the law in 2017, the ACA has remained more popular than ever, with more adults expressing a favorable than an unfavorable opinion.

In addition to providing information about the public’s evolving opinion and awareness of the law, surveys also helped provide information about people’s experiences under the law. For example, a 2014 survey of people who purchase their own insurance found that 6 in 10 people enrolled in insurance through the new marketplaces were previously uninsured, and that most of this group said they decided to purchase insurance because of the ACA. Subsequent surveys showed that most marketplace enrollees were satisfied with their plans, but many reported challenges related to the affordability of coverage and care.

These are just a few examples of the ways surveys helped provide insights into the dynamics of a complex health policy at different points in time.

Example #2: Understand the limits of public support of Medicare-for-All proposals

Another health policy issue where polls have provided useful information is the debate over a national, single-payer health plan. While the idea has been discussed for decades, public discussion was prominent most recently during the 2016 and 2020 Democratic presidential primaries, when Senator Bernie Sanders made “Medicare-for-all” a centerpiece of his campaign. Since 2017, a majority of U.S. adults have supported the idea of a national Medicare-for-all plan, but once again, polls also indicated why such a proposal had never become a political reality. For example, the public’s reaction to the idea varies considerably based on the language used to describe it; while majorities view the terms “universal coverage” and “Medicare-for-all” positively, most have a negative reaction to “socialized medicine,” and many are unsure how they feel about the term “single-payer health insurance.” Surveys also demonstrate that while support starts out high, many people say they would oppose a Medicare-for-all plan if they heard common arguments made by opponents, such as that it would lead to delays in treatments, threaten the current Medicare program, or increase taxes. Polls like these and others that test different messages can help shed light on the public’s likely reaction to real-world debates over policies, helping us understand some of the reasons why certain policies that seem to attract majority support in the abstract face an uphill battle once public debate and discussion about them begin.

Example #3: Understanding the impact of the Supreme Court’s overturning of Roe v. Wade

Polls can also help shed light when sudden events create policy changes that immediately affect individuals’ access to health care in different scenarios. A recent example is the Supreme Court 2022 decision in Dobbs v. Jackson that overturned Roe v. Wade and eliminated the nationwide right to abortion that had been in place since 1973. The Dobbs decision opened the door for states to pass their own abortion regulations, and many states had previously established “trigger laws” that made abortion illegal as soon as Roe was overturned.

Polls before and after the 2022 midterm election indicated how the overturn of Roe affected voter motivation, turnout, and vote choice. For example, polling in October 2022 showed abortion increasing as a motivating issue for voters, particularly among Democrats and those living in states where abortion was newly illegal. And election polling of voters showed how the Supreme Court decision played a key role in motivating turnout among key voting blocs that likely contributed to the Democratic party’s stronger-than-expected performance in the midterms. Two years later, amid growing economic concerns, polls leading up to the 2024 election showed that while the economy and inflation were far and away the top issues for voters, some key groups of women voters as well as voters in states with abortion-related ballot initiatives continued to be motivated by the issue of abortion more than two years after the Dobbs decision.

Understanding the impact of Dobbs is an area where polling of specific populations (including grouping individuals by the abortion laws in their state) is more useful than looking at the U.S. population as a whole. For example, in addition to shedding light on the dynamics of abortion as an election issue, polling in 2023 indicated widespread confusion about the legality of medication abortion, particularly among people living in states that had banned or severely limited the procedure. Surveys also shed light on the experiences of people living in different states; for example, a 2024 survey found that 1 in 5 women of reproductive age (18-49) living in states with abortion bans said either they or someone they know had difficulty accessing an abortion since the Supreme Court overturned Roe v. Wade due to restrictions in their state.

Example #4: Amplifying the voices and experiences of marginalized populations

Well-designed surveys of under-represented groups can provide important information about health policy by amplifying the opinions and experiences of those whose voices are often left out of policy debates. Examples include:

  • A survey of 2023 Medicaid enrollees documented the coverage status of people who were disenrolled during the Medicaid “unwinding” process. Beginning in March 2020, states kept people enrolled in Medicaid without the need to renew or re-determine eligibility under a law passed in response to the COVID-19 pandemic. When the law expired in March 2023, it was uncertain how individuals and families would be affected. Surveys like this helped document the impact of the policy change on people’s coverage status and access to care.
  • A survey of U.S. immigrants shed light on the health and health care experiences of a group that makes up one-sixth of the adult population. Among other findings, this survey showed that half of all likely undocumented immigrants in the U.S. lacked health insurance coverage, information not previously available from other data sources. It also illustrated the importance of state policies in determining coverage rates for immigrant adults, documenting the much higher uninsured rate among immigrants living in states with less expansive coverage policies (like Texas) compared to those in states with more expansive policies (like California).
  • A survey of trans adults documented this population’s struggles accessing appropriate health care. Among other findings, this survey found that almost 4 in 10 trans adults said it was difficult to find a health care provider who treats them with dignity and respect, 3 in 10 said they had to teach a provider about trans people in order to get appropriate care, and 1 in 5 had health insurance that would not cover gender-affirming treatment. Importantly, these survey findings help increase understanding of the health care experiences of a group that is often marginalized in U.S. society, and one that also faces other barriers, including economic challenges, higher rates of mental health challenges and unmet needs for mental health care.
  • A survey focused on racism, discrimination, and health showed the extent of discrimination and unfair treatment in health care settings. This survey found that large shares of Black, Hispanic, Asian, and American Indian and Alaska Native adults reported preparing for possible insults or being very careful about their appearance in order to be treated fairly during health care encounters. It also showed how individuals who have more visits with providers who share their racial and ethnic background report more positive health care experiences. These findings provide insights into possible policy solutions to improve care, highlighting the importance of a diverse health care workforce that is trained in culturally appropriate care.
  • Surveys of areas impacted by natural disasters also help provide information to guide recovery efforts in these areas. For example, a survey of Hurricane Katrina evacuees living in Houston-area shelters documented the physical and emotional toll of the storm and the disproportionate impact on lower-income, African American, and uninsured residents. A series of surveys of New Orleans residents in the years following Katrina showed steady progress in many areas of recovery, but highlighted how the gap between the experiences of the city’s Black and White residents grew over time in many ways. Surveys of Puerto Rico residents following Hurricane Maria and Texas Gulf Coast residents following Hurricane Harvey provided similar insights to shine a lens on disparities and highlight the needs of the local populations in those areas.

Resources

Copy link to Resources

Citation

Copy link to Citation

Brodie, M., Hamel, L., & Kirzinger, A., The Role of Public Opinion Polls in Health Policy. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-the-role-of-public-opinion-polls-in-health-policy (date accessed).

The Regulation of Private Health Insurance

Table of Contents

Introduction

Copy link to Introduction

Private health coverage is subject to significant requirements at the state and federal levels. While the Affordable Care Act (ACA) of 2010 ushered in many new requirements for the federal regulation of private health coverage, another federal law, the Employee Retirement Income Security Act (ERISA), has for over 50 years regulated the most predominant form of health coverage for people under age 65, employer-sponsored coverage.

States have traditionally been the primary regulators of health insurance, and state health insurance protections continue to play a major role alongside a growing list of federal protections aimed at addressing a variety of consumer concerns, including access to coverage, affordability, and adequacy. This chapter describes the landscape of laws and regulations that address health care coverage and the complicated interactions between state and federal requirements that can make these protections challenging for consumers to navigate. In this chapter, it is not possible to cover every single state and federal requirement for private plans, so the focus is on the primary laws and regulations that apply to private insurance coverage.

Timeline of Major Federal Laws for Private Health Insurance (Scatter Plot)

What Is Private Health Insurance?

Copy link to What Is Private Health Insurance?

Private health coverage is a mechanism for people to finance the health care services and medications they need, protecting them from the potentially extreme financial costs of this care.

At its core, health coverage is a financial contract between a private organization insuring the risk of loss and a policyholder. Where those insuring the risk or paying health claims are private entities such as insurance companies or private employers, this coverage is considered “private.” Coverage available in Health Insurance Marketplaces created by the ACA is considered private coverage, even though the Marketplaces are administered by state or federal government agencies. Public coverage, by contrast, involves financing arrangements for programs such as Medicare and Medicaid, which are paid primarily from public sources. This includes private plans participating in Medicare Advantage and Medicaid managed care arrangements. (See the chapters on Medicare and Medicaid for more information.)

A fundamental concept for the private provision of health coverage is pooling the health care “risk” of a group of people to make the costs of coverage more predictable and manageable. The goal typically is to maintain a risk pool of people whose health, on average, is the same as that of the general population. Private health coverage regulation has historically included steps to prevent insurers and plan sponsors from avoiding people in poor health, while also ensuring that risk pools include people in good health to guard against “adverse selection.”

A risk pool with adverse selection that attracts a disproportionate share of people in poor health, who are more likely to seek health coverage than people who are healthy, will result in increased costs to cover those in the pool, leaving those in better health to seek out a pool with lower costs.

Sources of private coverage. An individual with private coverage generally obtains it through one of two sources, either through their employer (“group” coverage) or by directly purchasing it from an insurer (“nongroup” coverage). Other related sources of coverage don’t exactly fit into one of these two categories, such as coverage provided by professional associations.

1. Employer coverage: In 2023, about 165 million people under age 65 had coverage through an employer. Employer-sponsored coverage is offered to eligible employees and usually to employees’ dependents, such as spouses and children. This coverage is referred to as “group” coverage, which is further broken down into small-group or large-group depending on the number of employees (Figure 1).

Private employers who “sponsor” group health plan coverage could include a range of entities, from a single nationwide retail employer with thousands of employees in many states to a small “mom and pop” operation with a handful of employees in one location. A single union can also be a group health plan sponsor of private coverage as an “employee organization,” as well as entities called “multiemployer” plans that are collectively bargained entities run by a joint board of trustees from labor and management that oversee collectively bargained benefits provided to employees of more than one employer, often in the same industry (for example, hotel workers or skilled workers in the building trades).

Public employers—federal, state, or local government—also sponsor group health coverage. The Federal Employee Health Benefit (FEHB) Program is the largest employer-sponsored health plan in the US. State and local government health plans are often referred to as non-federal governmental plans.

Employers, private and public, have at least two approaches to make coverage available to employees:

  • Fully-insured. An employer can purchase coverage from an insurer to cover their employees for a set premium. In this “fully-insured” arrangement, the insurer bears the financial risk if that group of employees ends up costing more than expected; these plans are regulated by the state in which they are sold. Each state has a group market for the sale of health insurance that is divided by size of the group for oversight and regulation: large group and small group.
    • Large Group Insurance Market typically involves insurance products sold to employers with 51 or more individuals (employees).
    • Small Group Insurance Market is generally an employer group of 50 or fewer individual employees. Small employers can purchase small group coverage from an insurer or through the state’s health insurance exchange or Small Business Health Options Program (SHOP). In a handful of states, the SHOP is the only place where a small employer can purchase state-regulated small group insurance coverage.
  • Self-insured. Employers can also use a “self-insured” (also often referred to as “self-funded”) arrangement where the employer assumes the financial risk by directly paying all covered claims. The employer typically contracts with a third-party administrator (TPA) to administer benefits by paying claims, designing benefits, establishing provider networks, and coordinating other aspects of coverage. TPAs are some of the same private organizations that provide health insurance as another line of business, as well as organizations called Pharmacy Benefit Managers (PBMs) that administer prescription drug benefits. As a result, coverage may not appear different to the covered worker than if they had fully-insured coverage. As explained in an upcoming section, unlike fully insured health coverage, self-insured coverage provided by private employers is largely not subject to state law but is governed primarily by federal law---mainly ERISA. Self-insuring health benefits are more common among larger employers because they can spread risk over a larger number of enrollees.

2. Individually-purchased insurance coverage: An individual can purchase private health coverage for themselves and their family without the involvement of their employer, referred to as “nongroup” coverage. Every state has an “individual insurance market” that consists of the following:

  • Marketplace. The ACA required the creation of health insurance Marketplaces in each state, where individuals can purchase insurance, with federal financial assistance for premiums and cost sharing if eligible. The coverage purchased from a Marketplace must meet certain minimum standards, including coverage of essential health benefits, no preexisting condition exclusions, and limits on varying premiums based on health status (“ACA-compliant” insurance). (See the ACA chapter for more information.)
  • Off Marketplace. People can also purchase individual insurance outside the Marketplace where federal financial assistance is unavailable. This could include ACA-compliant plans similar to those offered on the health insurance Marketplaces, and other types of coverage or financial products with lower premiums, but less comprehensive coverage than ACA-compliant plans, such as short-term limited duration coverage, fixed and hospital indemnity arrangements, health care sharing ministries, and others.

3. Other Sources of Private Health Coverage: Other sources of health coverage subject to unique regulatory standards include health coverage provided through entities called “multiple employer welfare arrangements” (MEWAs), “church plans,” and coverage provided by colleges and universities for their students.

  • A MEWA is generally any arrangement that provides benefits – in this case, health benefits – to employees of more than one unrelated employer. Historically, MEWAs have been vehicles for organizations to market less expensive health benefits to groups of employers, especially small employers. To address a history of MEWA insolvencies attributed to a lack of proper government oversight, changes to ERISA in 1983 created a complicated regulatory regime just for MEWAs, subjecting them to a mix of federal and state laws.
  • One type of MEWA, also governed by ERISA, allows groups of more than one employer to sponsor health coverage for their employees, known as an “Association Health Plan.” Traditionally, these types of plans have been available to groups of small employers in a similar industry, such as those who sell real estate or work in a similar profession. In recent years, federal efforts to expand the criteria for what types of employers may form an AHP have been the subject of litigation and regulations.
  • Church plans are offered to employees by a church or association of churches, including entities controlled by or associated with a religion, such as religiously-affiliated hospitals and schools. Unlike other employer-sponsored plans, church plans are exempt from most ERISA requirements and some of the ACA’s health reforms. These regulatory gaps in church plans, including coverage of contraception, have been the subject of numerous legal proceedings.
  • A student health plan is any health coverage sponsored by a college or university for students. While it is not group coverage, it can be sponsored by a university in the same way employers sponsor health coverage. The ACA has special rules for this coverage. While an insured arrangement is considered individual market coverage, exceptions allow it to be provided without the insurer having to meet certain ACA market rules. A university can also sponsor a self-insured health plan for students. These arrangements do not have to meet the ACA’s market rules, although states may regulate them.

What Are the Different Types of Private Health Plans?

Copy link to What Are the Different Types of Private Health Plans?

Most private plans utilize a “network” of health care providers and hospitals, with some plans requiring a referral from a primary care provider (PCP) for enrollees to see a specialist. These types of arrangements, referred to as “managed care plans,” attempt to control costs and utilization through financial incentives, development of treatment protocols, prior authorization rules, and (in limited circumstances) dissemination of information on the quality of provider practices. Most private health coverage, whether employer-sponsored or individually purchased, falls into one of the following types:

Types of Private Insurance Plans (Table)

All of these plan types are available in the individual market, both on and off the Marketplace. Most employers that offer health benefits offer just one type of health plan, though larger firms may offer more. PPOs are the most common type of health plan offered by employers.

Other employer-sponsored health coverage arrangements: Employers also can offer a Health Reimbursement Arrangement (HRA), which is an employer-funded group health plan, sometimes paired with a high-deductible health plan (HDHP), that reimburses an employee up to a certain amount for qualified medical expenses and, in some instances, health insurance premiums. Reimbursements are tax-free to the employee, and amounts in the account can carry over to the following year, but employees lose any amounts when they leave the employer. Other variations of HRAs include an Individual Coverage HRA (ICHRA), where an employee can use funds in the HRA to purchase individual insurance either on or off the Marketplace. Qualified Small Employer Health Reimbursement Arrangements (QSEHRAs) are HRAs that certain small employers can make available for tax-free reimbursement of certain expenses.

Health Savings Accounts (HSAs): HSAs are tax-advantaged savings accounts that enrollees in certain HDHPs can use to pay for qualified medical expenses. While the HDHP associated with an HSA is usually sponsored by an employer or obtained through a Marketplace plan, the HSA itself is not usually considered employer-sponsored coverage (in contrast to HRAs). HSAs are owned by the individual and are portable, meaning consumers can carry them from job to job and use them after retirement.

Value-Based Arrangements: Some private health plans utilize “value-based” coverage and alternative payment models. These designs, primarily used in federal Medicare and Medicaid demonstration projects, aim to make providers more accountable for patient outcomes through various financial and other incentives. The objective of value-based care design is to shift the fee-for-service reimbursement model of paying for care based on “volume” to a system that pays based on the “value” of a service. Demonstration results to date have not shown major savings, but these designs are still discussed as a potential cost-containment tool for private health coverage. Payers and providers have also looked to value-based payment models to improve health disparities and to provide more patient-centered care.

How Do Federal and State Regulation of Health Insurance Interact?

Copy link to How Do Federal and State Regulation of Health Insurance Interact?

The regulatory framework for private health coverage has evolved into a complicated system of overlapping state and federal standards. This federalism framework creates a sometimes precarious “marriage” between state and federal authority in order to implement health policy goals.

At a high level, key aspects of the regulatory framework include the following five features: (Table)
1. States lead on insurance regulation, but with a federal fallback for most protections.

The regulation of insurance has traditionally been a state responsibility. States license entities that offer private health insurance and have a range of insurance standards, including financial requirements unique to state law. However, the federal government has played an increasingly significant regulatory role over the past 50 years.

The federal pension law, ERISA, passed in 1974, applies to insured and self-insured private employer-sponsored health coverage with similar legal and enforcement mechanisms to protect individuals covered by private group health plans as those created for pension plans.

Separately, the federal Health Insurance Portability and Accountability Act of 1996 (HIPAA) created new federal requirements and the basic framework for how state and federal law now interact. Under this “federal fallback” structure, states may require that insurers in the group and individual market (as well as state and local government self-insured plans) implement federal requirements on health coverage. If a state fails to “substantially enforce” the federal requirements, the federal government will enforce those protections. The federal fallback framework was intended to allow states to continue to regulate private coverage while ensuring that all consumers nationwide have a floor of federal protections when a state fails to implement them.

The federal fallback framework does not apply to self-insured employer-sponsored coverage. The U.S. Department of Labor (DOL) almost exclusively regulates private self-insured employer-sponsored plans. The Center for Medicare and Medicaid Services (CMS) directly enforces federal protections against state and local government self-insured employer plans (although states can also do so).

2. ERISA limits the application of state law for those with private employer-sponsored coverage.

ERISA specifically “preempts” or prevents state law from applying to most self-insured group health plans, limiting the scope and application of state protections for many Americans covered by employer-sponsored plans.

Aspects of this preemption have been the topic of almost 50 years of litigation, resulting in three overall conclusions:

  • Most state insurance laws, including state benefit mandates, don’t apply to self-insured ERISA plans, resulting in fewer regulatory requirements on these plans than on fully-insured plans.
  • State insurance laws generally do apply to fully-insured ERISA plans.
  • ERISA provides exclusive, yet limited, civil remedies for enrollees in ERISA plans who are harmed due to a violation of the law.

Today, some argue that ERISA preemption sustains the employer-based health coverage system because meeting an ever-growing list of state laws would be costly for employers, particularly those with employees in multiple states. Having national uniform standards, they argue, provides employers with an incentive to offer coverage. Others argue that preemption handcuffs states’ ability to protect consumers and control health care costs and that it is no longer needed given the ACA’s employer shared responsibility provision for larger employers and the increased regulation that applies a variety of rules to both fully-insured and self-insured plans. Prospects for change are limited, but some have explored the possibility of alternative approaches.

3.  Federal regulation of private health coverage can differ based on the market/source of coverage.

Private health insurance regulations vary based on the insurance market and the source of coverage. This is in part due to ERISA preemption and the ACA, which applies many reforms only to the individual and small-group markets.

Further complicating this are plans that existed before the ACA was passed, called “grandfathered” plans, that do not have to meet many of the ACA standards, so long as no significant changes in cost sharing and benefits are made to the plan.

The ACA did, however, alter federal law to create a large number of consumer protections that apply many of the same regulatory requirements across almost all sources of private health coverage. (See Table 7.)

Finally, some federal standards only apply to employer-sponsored plans (insured and self-insured) that are governed by ERISA, such as the requirement on employers with 20 or more employees to provide temporary continuation of coverage in certain situations, known as COBRA, which also applies to certain state and local government employers. There are also obligations on plan “fiduciaries” that are unique to ERISA plans.

This all means consumers can have different legal protections with their private coverage based on their coverage type and the state where they live.

4. Special exceptions in regulations allow certain types of private coverage to avoid having to meet many insurance protections.

Some private plans are specifically exempt from most federal private health coverage protections, including the ACA. These forms of coverage are often called “non-ACA compliant” coverage. While “non-ACA compliant” does not automatically mean it is illegal or inappropriate, some forms of this coverage have come under increasing scrutiny by federal and state authorities due to their gaps in consumer protections.

These types of coverage fall into these general categories:

  • Coverage that is an “excepted benefit” is specifically carved out of most of the ACA and other federal requirements. Some are considered health coverage under federal law, such as certain dental and vision benefits, and other forms of coverage may not be, such as fixed and hospital indemnity, cancer-only coverage, accidental death and dismemberment, and long-term care coverage. (This Health Affairs article provides a more detailed description of excepted benefits.)
  • Short-term limited-duration coverage and other forms of coverage are not regulated as health insurance under federal rules (as mentioned in the previous section).
  • Employer-sponsored plans with less than two participants who are current employees. This exception was included in the 1996 HIPAA law and has been interpreted as excluding employer-sponsored plans that cover only retirees from many federal insurance requirements.

Some of these forms of coverage are the focus of business promoters looking to market cheaper, largely unregulated forms of coverage. In some instances, this coverage might be promoted by unscrupulous actors who falsely market the coverage as meeting ACA requirements or as providing comprehensive coverage. In other cases, coverage is sold as supplemental “health” coverage along with ACA-compliant health insurance, sometimes with very high deductibles. These exceptions to the ACA’s broad coverage requirements can operate as loopholes in the implementation of consumer health coverage protections and may create ambiguities for consumers as well as employers.

5. Tax regulation matters for cost and access to health care and coverage.

Central to evaluating how private coverage works are the tax subsidies that reduce the cost of coverage and benefits, which can incentivize employers to sponsor and individuals to purchase private health coverage. Tax regulations also interpret what medical expenses (as opposed to general wellness or other non-medical expenses) get a tax preference.

The largest health care tax subsidy is applied to employer-sponsored coverage. Tax-exempt employer contributions for medical insurance premiums and medical care resulted in more than $224 billion in lost revenue for the federal government in 2022. Employer-sponsored health coverage is excluded from federal income tax, as well as federal employment taxes (and equivalent state taxes). The exclusion also applies to amounts reimbursed to employees by an employer under arrangements called “health flexible spending arrangements” (health FSAs), where an employee elects to have amounts withheld from their wages to pay for medical expenses. The exclusion provides considerable tax savings for employers and employees making contributions toward health coverage. The value of this exclusion increases as income increases, making income tax savings greater for higher-income individuals than for lower-income individuals. For various policy reasons, including to rein in health care costs, there have been efforts to change or cap this exclusion over the years, but to date, none have been successful. The most recent, the “Cadillac tax” provision of the ACA, was removed from the law before it was implemented (see the Employer-Sponsored Health Insurance chapter).

Additionally, the ACA created refundable tax credits based on household income to help individuals purchase coverage on a health insurance Marketplace (see the Affordable Care Act chapter). In contrast to the employer exclusion, tax subsidies for Marketplace participants are higher for those with lower incomes. Temporary increases in these credit amounts, passed as part of the American Rescue Plan and the Inflation Reduction Act, have led to record Marketplace enrollment. Unless Congress extends them, the temporary increases expire at the end of 2025. Unlike employer-sponsored insurance, Marketplace enrollees who pay a premium for their individual market insurance coverage generally do so with after-tax dollars (although an employer can sponsor tax-advantaged ICHRAs or QSEHRAs, as described above, to help employees pay for Marketplace and other individual market coverage).

In addition to the tax advantages related to employer-sponsored health coverage and tax subsidies received by lower-income individuals with Marketplace coverage, HSAs bring their own set of tax advantages for those who use funds in the account to pay for cost sharing and for items the IRS includes as qualified medical expenses. In 2025, a federal budget reconciliation law was enacted that may increase the use of HSAs.

What Federal Requirements Apply to Health Insurance?

Copy link to What Federal Requirements Apply to Health Insurance?

The scope and extent of federal regulation affecting private health coverage has vastly increased, especially with the passage of the Affordable Care Act (ACA) in 2010. The ACA largely retained the framework for the regulation of private coverage, adding a long list of new provisions to different regulated pieces of our fragmented health care system. This means specific and overlapping requirements on insurers, employer-sponsored plans, and, more recently, in the No Surprises Act, also on providers.

The ACA also unleashed a firestorm of activity resulting from longstanding political and philosophical differences on the role of federal government regulation of health care. Efforts to repeal and replace the ACA in 2017, several U.S. Supreme Court cases challenging ACA provisions, and hundreds of other cases in the lower courts on the ACA and other federal requirements mean the law in this area has and will continue to be in flux.

Regulatory priorities can and have shifted depending on what party controls the White House and Congress, resulting in ever-changing federal standards. This section reviews the current landscape of federal requirements. A discussion of every single relevant federal regulation is beyond the scope of this chapter, but the major requirements have been divided into six categories:

  • Access to health coverage
  • Affordability of health coverage
  • Benefit design and adequacy
  • Reporting and disclosure of information concerning coverage
  • Review and appeal of health claims
  • Other federal standards
1. Access to coverage

Federal health care reform has prioritized expanding health coverage to those without it for quite some time, especially for those not eligible for a public program such as Medicaid or Medicare, or who do not have coverage through their current employer. Prior to the passage of the Affordable Care Act in 2010, state laws and regulations were designed to address the potential for adverse selection in health insurance by allowing insurers to engage in certain practices such as “underwriting,” which allowed insurers in the individual and group markets to decline to cover or renew coverage due to a person’s health status or a group’s claims history, and helped plans maintain predictable and stable risk pools. Further, an insurer could cover the applicant, but charge a higher premium based on age, health status, gender, occupation, or geographic location. In addition, insurers could exclude benefits for certain health conditions if the person was diagnosed or treated for that condition before becoming insured (a “preexisting condition exclusion”).

States made some reforms, particularly in the small group market, to address these barriers to coverage. Some of these changes became part of the federal Health Insurance Portability and Accountability Act (HIPAA) of 1996. However, it was not until the ACA that the regulation of private insurance, at least for the individual and small group markets, was fundamentally changed.

Core Private Insurance Coverage Protections. The ACA established core market rules designed to expand coverage to most people in the U.S. New ACA legal requirements include:

Table summarizing major consumer protections in private health insurance coverage. The protections include guaranteed issue, which requires plans to accept eligible applicants; guaranteed renewability, which generally requires plans to renew coverage except in limited circumstances such as fraud or nonpayment of premiums; bans on using health status or genetic information to determine eligibility or premiums in the individual and small-group markets; restrictions on premium variation, allowing differences only based on factors such as age, tobacco use, geographic area, and enrollment type; prohibitions on pre-existing condition exclusions; and prohibitions on rescissions, preventing plans from retroactively canceling coverage except in cases of fraud or intentional misrepresentation.

Requirements for premium stabilization and other efforts to protect the risk pool. The ACA’s private insurance market regulations also ushered in concerns that its protections, including guaranteed issue and the elimination of health underwriting for some coverage, would result in adverse selection (discussed in the first section). Regulatory efforts to prevent adverse selection have also focused on certain plans and products that do not have to meet most of the ACA rules, such as short-term limited-duration plans. Non-ACA-compliant coverage may be attractive to consumers looking for lower monthly costs, but these plans can leave consumers underinsured and may compromise the risk pool by drawing out healthier individuals.

Federal guidance and regulation aimed at protecting the risk pool as part of the ACA include:

Table summarizing Affordable Care Act provisions designed to protect and stabilize insurance risk pools. The table highlights three key approaches: the individual mandate, which originally required most U.S. citizens and legal residents to maintain minimum essential coverage and still affects eligibility for certain special enrollment periods; premium stabilization programs, including temporary reinsurance and risk corridors and a permanent risk adjustment program to reduce uncertainty in the individual and small-group markets; and the employer mandate, which requires large employers to offer affordable health coverage meeting minimum value standards or potentially face penalties when employees receive Marketplace premium tax credits.

Standards to prevent coverage gaps. Access to coverage is also enhanced by federal requirements to provide for the continuity of coverage or care to prevent gaps for those who do or could lose coverage, including:

Table outlining key private insurance protections designed to prevent interruptions in health coverage. Protections include dependent coverage for young adults up to age 26, continuation coverage under COBRA for people who lose coverage because of events such as job loss, reduced work hours, or divorce, special enrollment periods that allow individuals to enroll in or change coverage after qualifying life events outside the regular open enrollment period, and continuity-of-care protections that allow some patients to continue receiving care from a provider who leaves their plan’s network. The table emphasizes mechanisms that help individuals maintain or transition health coverage when life circumstances change.
2. Financial Protection and Affordability

High costs, in the form of both premiums and cost sharing, have been a defining feature of employer-sponsored and individually-purchased (for unsubsidized enrollees) health coverage. Federal reforms have sought to address the stability and affordability of health insurance. Key provisions include:

Federal Insurance Financial and Affordability Protections (Table)
3. Benefit Design and Adequacy

Federal requirements also include a list of minimum standards for how a plan is designed or operated in an effort to ensure that enrollees have coverage that is comprehensive enough to cover medically necessary care, with processes that do not unnecessarily limit access to covered benefits. Such requirements include laws that prohibit plans from imposing annual dollar limits on coverage or requiring waiting periods longer than 90 days before employer-sponsored coverage kicks in. States may have additional benefit mandates for state-regulated plans, such as comprehensive coverage requirements for mental health or substance use disorders or fertility services.

Required coverage.

The ACA requires all private, non-grandfathered health plans to cover preventive services with no cost sharing for enrollees. These requirements change over time as preventive service recommendations are updated and new services are added. In general, these include:

Table summarizing federal requirements for preventive services coverage in private health insurance plans. The table explains that covered preventive services generally fall into four categories: services rated A or B by the U.S. Preventive Services Task Force, recommended immunizations for children and adults, preventive care for children and adolescents supported by the Health Resources and Services Administration, and women’s preventive services, including contraception and screenings, identified by the Women’s Preventive Services Initiative. The table highlights the major categories of preventive care that private health plans are required to cover.

The preventive care coverage requirement has been the subject of extensive litigation since the ACA was passed. KFF briefs provide more detail on this litigation and a 2025 U.S. Supreme Court decision involving ACA preventive care standards. The contraceptive coverage requirement has been the topic of two U.S. Supreme Court cases and several regulations, now allowing employers to not cover contraception if they have a religious objection.

Other required design standards across most health plans.

Large group, small group, individual, and self-insured health plans are required to abide by other benefit design standards that aim to contain out-of-pocket costs and improve access to quality care. These design standards include:

Design Standards That Apply to Most Health Plans (Table)

Design standards limited to individual and small group plans. Federal requirements on health plan design standards for certain segments of the individual and small-group markets have evolved since the ACA was passed. Plans must meet these rules as part of annual certification requirements for qualified health plans. Examples of these standards include:

Design Standards for Individual and/or Small Group Health Plans (Table)
4. Disclosure, Reporting and Transparency

The 2023 KFF Survey of Consumer Experiences with Health Insurance found that most Marketplace and employer-sponsored insurance (ESI) enrollees reported difficulty understanding some aspect of their health insurance compared to consumers enrolled in Medicaid and Medicare:

Grouped bar chart comparing the share of insured adults who say key aspects of their health insurance are somewhat or very difficult to understand across employer-sponsored insurance (ESI), Marketplace, Medicaid, and Medicare coverage. Marketplace enrollees are most likely to report difficulty understanding what their insurance covers (46%), out-of-pocket costs (41%), and explanations of benefits (38%), followed by ESI enrollees (40%, 34%, and 35%, respectively). Smaller shares of Medicaid and Medicare enrollees report difficulty with these topics. Across all coverage types, understanding what insurance will and will not cover is the aspect most commonly cited as difficult, indicating that many insured adults struggle to understand important features of their health coverage.

Lack of information or understanding about key features of an individual’s health coverage can put patients at financial risk and result in negative health outcomes. Employers and other health purchasers have also struggled to get the information they need to make prudent decisions about cost-effective coverage options and hold their service providers accountable for their plan designs, contracting, and administration activities. Regulations have increased over time to make more information available to enrollees or prospective enrollees, as well as to federal agencies to conduct their oversight responsibilities. What to disclose and how much information is useful is a continuing policy challenge.

Most federal disclosure, reporting, and transparency requirements fall into two categories: Disclosure of information to enrollees and/or the public (Table 9) and reporting to the federal government (Table 10). Note that the requirements provided in these tables are not exhaustive, but include examples of some of the main reporting, disclosure, and transparency requirements that plans, providers, and facilities are subject to.

Disclosure of Information to Enrollees and/or the Public (Table)

Ongoing reporting by private plans to federal agencies is a tool for agency oversight to assess compliance with regulations and evaluate trends. In some instances, agencies are required to use this information to report aggregate information to the public and Congress.

Requirements for Reporting to the Federal Government (Table)
5. Claims and Appeals Processes

Access to a fair system of review for consumer grievances about plan actions and claims denials has been a key element of federal consumer protection.

A 1997 Clinton Administration initiative, the Patient Bill of Rights, resulted in several federal agencies taking regulatory actions to enhance consumer protections for patients and workers. As part of this initiative, the DOL updated claims and appeals rules that applied to private-sector employer plans regulated by ERISA to make the claims review process:

  • Faster (shortened timeframe for plans to make a decision on claims and appeals)
  • Fairer (ensure plan decision makers were free of conflicts of interest)
  • Fuller (more transparent through the disclosure of more information to consumers–including language access standards–about the reason for a claim denial)

The DOL issued regulations in 2000 governing the “internal” claims review process, conducted internally by a plan or plan-sponsor employer. For the first time, these updated rules accounted for managed care features such as prior authorization, where health plans determine medical necessity before the plan covers an item or service, requiring, for example, shorter time frames for claim decisions and appeals for these “pre-service” claims.

Table summarizing timelines for private health plans’ to notify consumers of internal appeals decisions. Enrollees generally have 180 days to file an internal appeal regardless of whether the appeal is urgent, pre-service, or post-service. Plans must make decisions and notify consumers on urgent appeals within 72 hours. For pre-service appeals, plans must issue a decision within 30 days for a single appeal and within 15 days for a second-level appeal. For post-service appeals, plans must issue a decision within 60 days for a single appeal and within 30 days for a second-level appeal. The table highlights the shorter time frame for urgent appeals and pre-service claims (prior authorization decisions) compared to claims for services already provided.

These rules were the basis for reforms applied across all private health coverage in the ACA. These reforms established a federal floor of protections for the internal claims and appeals process and added an option for consumers to appeal denied claims through an “external review” by an entity independent of the plan. Only certain types of claims, such as those that involve clinical judgment, are eligible for external review.

Policymakers have renewed scrutiny of the prior authorization process, as well as claims review and appeals generally. Claims and appeals standards that apply to Medicare Advantage plans, Medicaid, and some Marketplace plans were updated in 2024 to reduce delays in decision-making and to provide more transparency about the outcomes of claims and appeals decisions.

6. Other Federal Standards

Several other federal laws and regulations provide consumer protections in private health insurance, often indirectly, that sometimes have stronger enforcement mechanisms and penalties than federal insurance laws. These include:

Civil Rights Law. The Civil Rights Act of 1964 (and later amendments to it, including the Pregnancy Nondiscrimination Act) and the Americans With Disabilities Act of 1990 created protections against discrimination based on race, color, national origin, sex, age, and disability. At a minimum, these standards apply to employers with 15 or more employees, and, in effect, regulate those employers’ group health plan coverage.

Section 1557 of the ACA is a nondiscrimination provision that potentially applies many existing civil rights laws directly to health care entities, including insurers that receive federal funds. The extent of its reach has been the subject of several sets of regulations, with the iteration issued by the Biden administration addressing Section 1557’s ban on sex discrimination (among other issues) and reinstating protections against discrimination for LGBTQ+ people seeking health care and coverage, including for gender-affirming care. Trump administration actions will likely seek to undo this requirement and place restrictions on gender affirming care that the courts will be tasked with evaluating in the years to come.

Antitrust Laws. Antitrust laws in health care prohibit anticompetitive practices and mergers by health care providers, hospitals, and insurers, which can reduce competition and increase prices. As provider consolidation increases, federal agencies such as the Department of Justice (DOJ) and the Federal Trade Commission (FTC) have engaged in enforcement initiatives in recent years. Health insurers have also faced antitrust scrutiny as the market shares of the largest health insurers continue to dominate in most locations. Oversight of pharmacy benefit managers, now mostly owned by or affiliated with the largest health insurers, is one area of focus where Congress continues to debate whether additional standards are warranted, and state attorneys General are increasingly focusing their attention.

Privacy Laws. As digital health technology has advanced, so have concerns about protecting consumer health information, as the fast development of new technology (e.g., health-related apps, artificial intelligence) has made it difficult for regulation to keep up. The leading federal privacy requirements for health plans’ use of certain patient information, set out in HIPAA regulations, are now almost 25 years old. Efforts to update this regulation have been discussed, but have not yet been finalized. Updates to the HIPAA privacy rules were proposed toward the end of the first Trump administration. Updates to HIPAA’s security standards were proposed at the end of the Biden administration. It is unclear whether renewed proposals in this area are imminent. Regulatory changes to HIPAA in 2023 aimed at clarifying reproductive health care privacy were struck down by a federal court in 2025. The FTC has sought to regulate areas not covered directly by HIPAA, such as software applications increasingly marketed as part of health coverage. Continuing federal efforts to advance electronic information sharing (known as "interoperability") will mean renewed calls for increased federal privacy and security protections.

Special privacy protections for substance use disorder information are regulated under a law known as “Part 2.” This law aims to protect the confidentiality of this information while still allowing providers to share patients’ mental health and substance use disorder information with plans and others to coordinate care and administer benefits.

Gag Clauses. Plans and issuers are prohibited from entering into an agreement with a provider, third-party administrator, or other service provider (including pharmacy benefit managers) that restricts the plan and issuer from accessing claim, cost, or quality information on providers, enrollees, plan sponsors, and other entities, known as a “gag clause.” Plans and issuers must annually submit an attestation of compliance with these requirements to the federal government.

Who Regulates Health Insurance at the Federal Level?

Copy link to Who Regulates Health Insurance at the Federal Level?

Three federal agencies have overlapping jurisdiction for most federal regulation of private health plans: the U.S. Department of Health and Human Services (HHS), the U.S. Department of Labor (DOL), and the U.S. Treasury Department. Through a structure created by HIPAA in 1996, these three agencies jointly issue regulations and other guidance on laws passed by Congress that place the same or similar standards across all private plans.

The same or similar federal requirements for private health plans are typically contained in three separate statutes that each agency oversees:

As an example, if Congress passes a federal law that requires all insurers of individual and group coverage and all employer-sponsored plans to meet a certain standard, any regulations issued to implement that standard are usually issued jointly by HHS, DOL, and Treasury with separate but identical language added to the Public Health Service Act (PHSA), ERISA, and the Internal Revenue Code (IRC). However, each agency has its own requirements for how these laws are enforced. In addition to these overlapping authorities, each of these three agencies has exclusive federal authority over certain aspects of private health insurance regulation (though the federal authority might be shared with states in some instances):

Table summarizing which federal agencies enforce private health insurance requirements and the laws they oversee. The Department of Health and Human Services, primarily through CMS and the Center for Consumer Information and Insurance Oversight, enforces Public Health Service Act requirements, including Marketplace standards, federal consumer protections, and oversight of insurers when states do not substantially enforce federal standards. The Department of Labor, through the Employee Benefits Security Administration, administers and enforces ERISA requirements for employer-sponsored health plans, including reporting and disclosure rules, COBRA protections, fiduciary standards, and Affordable Care Act consumer protections. The Treasury Department, through the Internal Revenue Service, administers provisions of the Internal Revenue Code related to private health insurance, including Marketplace premium tax credits, employer responsibility requirements, health savings accounts, COBRA standards, and civil penalties.

Other agencies with important oversight roles of private health coverage include:

  • HHS’s Office of Civil Rights: Implements HIPAA’s administrative simplification standards; ACA section 1557 nondiscrimination rules
  • HHS’s Office of the National Coordinator: Coordinates efforts to implement and use health information technology and health information exchange
  • HHS’s Food and Drug Administration: Regulates clinical investigations and supervises the safety of pharmaceutical drugs, biological products, and medical devices
  • Department of Justice: Antitrust enforcement
  • Federal Trade Commission: Antitrust enforcement
  • Equal Employment Opportunity Commission (EEOC): Nondiscrimination in health coverage and wellness program standards

How Are Federal Health Insurance Requirements Implemented and Enforced?

Copy link to How Are Federal Health Insurance Requirements Implemented and Enforced?

As the executive branch of the U.S. government, the federal government has the authority to execute laws passed by Congress and signed by the President, including issuing regulations to operationalize and implement a statute. In addition, specific agencies have the authority to investigate violations of the law and enforce the law through policy form review, market conduct exams, assessment of penalties, and/or bringing a court action to stop an insurer from violating the law (called an injunction).

Regulations and Other Guidance

Process: The federal regulatory process is governed primarily by the Administrative Procedure Act (APA). This law, along with specific executive orders, governs the process known as “notice and comment rulemaking,” where regulations are proposed (through a notice of proposed rulemaking or “NPRM”) and are subject to public comment for a certain period of time and then finalized. The process is administered by the Office of Management and Budget (OMB), an agency within the Executive Office of the President. The OMB’s Office of Information and Regulatory Affairs (OIRA) coordinates the review and release of regulations from the agencies. Regulations are published in the Federal Register, a daily publication of regulations and notices. Information about regulations under OIRA review is available by agency at Reginfo.gov, and the public can view all regulations and comment letters at Regulations.gov. Twice a year, OMB issues a regulatory agenda of regulations agencies expect to publish in the coming months.

Authority: Once a regulation has gone through the notice and comment process and a final rule is issued, it is generally considered to have the force of law, meaning private actors must comply with it, and individuals can rely on having the protections set out in the law and the regulation. However, regulations are subject to legal challenge under the APA if they are inconsistent with the statute.

Review of regulations by courts: Traditionally, if a regulation interprets a part of a statute that was not clear as drafted by Congress, and a federal court reviews a challenge to the regulation, the court would uphold the interpretation in a regulation unless it is unreasonable or arbitrary. Essentially, courts deferred to the expertise of government regulators and the regulatory review process to uphold a regulatory requirement if they deemed the interpretation reasonable. This practice is called “Chevron deference,” named after a Supreme Court case from 1984, Chevron v. Natural Resources Defense Council, that set out the framework for court review of ambiguous language in a statute. This standard of review can result in agencies having discretion to implement policy changes through the interpretation of regulation. That discretion was challenged in recent years as too broad, giving regulators too much authority, and in June 2024, the U.S. Supreme Court overruled its previous decision, meaning federal courts are no longer required to defer to regulations of administrative agencies in circumstances where they traditionally would have. Eliminating Chevron deference could weaken the impact of regulation on public policy and shift more policy decisions to courts.

Sub-regulatory guidance: Other types of information and guidance commonly issued by a federal agency that do not go through the formal regulatory notice and comment process are referred to as “sub-regulatory.” Information and interpretation in sub-regulatory guidance usually do not have the force of law as regulations do, and typically do not create legally binding obligations on private parties. They are, however, useful in quickly communicating information to regulated entities and the public to signal how and when the agency plans to implement a new law, and the timing of that implementation. However, reliance on these types of guidance by consumers has its limits since regulated entities might still assert that this type of guidance is not binding on them. Examples of sub-regulatory guidance include:

  • Frequently asked questions, manuals, memos, and letters used by CMS, DOL, and the IRS: Certain provisions of the ACA have been the subject of numerous sub-regulatory guidance, including over 60 pieces of guidance in the form of frequently asked questions issued jointly by CMS, DOL, and the IRS. Sub-regulatory guidance also includes implementation manuals, policy letters, and enforcement memos.
  • Advisory opinion or information letters: The DOL and IRS have used advisory or information letters and chief counsel notices to address fact-specific questions at the request of regulated entities. DOL and IRS responses to these inquiries only apply to the specific parties and scenarios addressed, so they can’t be relied on by the public and can create ambiguities about what the law requires, which can remain unresolved for years until formal regulations are finalized. Note that the IRS also has several other types of guidance with varying levels of authority.

Enforcement

Given the federal fallback framework described in previous sections, the enforcement mechanism for most federal requirements on private coverage depends on the type of health plan and the federal agency enforcing the requirement, as summarized in Table 13 below.

Government enforcement. Under the existing federal fallback framework, CMS has developed a process for determining whether a state is substantially enforcing each specific federal insurance protection. This means that whether a state or CMS is responsible for enforcement can differ for each health coverage standard, resulting in a patchwork of federal and state enforcement responsibilities. In addition, both the DOL and the IRS each have their own separate enforcement processes for the federal standards they implement.

Private Right of Action and Remedies. Some laws also allow individual consumers or their representatives to bring a lawsuit independent of the government to address a violation. These laws may detail what types of “remedies” are available if the challenge is successful---for example, an injunction to stop a violation, a civil penalty, or compensatory or punitive damages. Without this “private right of action,” aggrieved consumers must rely solely on the government to act to address a violation of the law. Even federal laws, such as ERISA, that allow individual consumers to bring a lawsuit to resolve certain disputes, have limited remedies to address a violation. ERISA does not generally allow monetary damages as a remedy.

Table summarizing how enforcement of private health insurance requirements varies by plan type and regulatory authority. Self-insured employer-sponsored group health plans are primarily overseen by the Department of Labor and Treasury, which can investigate violations, impose penalties, and enforce ERISA requirements, while individuals may bring certain lawsuits to recover benefits. Nonfederal governmental employer-sponsored plans are overseen by CMS, which can investigate violations and impose penalties. Individual market plans are primarily regulated by state insurance departments, with CMS serving as a federal backstop when states do not substantially enforce federal standards. Large- and small-group insurance plans are subject to oversight by state insurance departments, CMS, and, in some cases, the Department of Labor and Internal Revenue Service. Across plan types, enforcement tools include investigations, market conduct examinations, civil monetary penalties of up to 0 per day per affected individual, and other remedies that vary depending on the plan and regulator.

The federal fallback framework also applies to most of the requirements on health care providers and facilities that are now part of federal law. In 2020, Congress passed and President Trump signed the Consolidated Appropriations Act (CAA), which includes new protections on balanced billing (the No Surprises Act) and various provider rules regarding disclosure and transparency. States are expected to enforce these standards against providers, with CMS as the federal fallback. State health departments or state agencies that oversee provider and facility licensing and practice standards oversee these rules. CMS has surveyed states and entered into collaborative enforcement agreements with each state, including which CAA rules the state is prepared to enforce and which ones CMS will need to implement. CMS can assess a penalty of up to $10,000 per violation against a provider or facility for non-compliance.

Enforcement of other standards. Outside of the above federal fallback framework, each agency has its own separate enforcement mechanisms for the laws it implements alone. For instance, HHS has the authority to assess fines under HIPAA privacy rules for violations, but individuals harmed by a HIPAA violation do not have a private right of action under that law. Enforcement processes and remedies available under federal nondiscrimination requirements under the Civil Rights Act or the Americans with Disabilities Act vary, but some include monetary damages in the form of compensatory damages.

Who Regulates Private Health Insurance at the State Level, and What Are the Primary Enforcement Tools Used?

Copy link to Who Regulates Private Health Insurance at the State Level, and What Are the Primary Enforcement Tools Used?

The McCarran-Ferguson Act, enacted by Congress in 1945, clarified that states have the primary role in regulating the business of insurance. Although changes have since been made to that law, states have several mechanisms in place to regulate insurance. States license entities that offer private health coverage in a process that reviews the insurer’s finances, management, and business practices to ensure it can provide the coverage promised to enrollees. States also license the insurance agents and brokers in the state (see the section “What Is the Role of Health Insurance Brokers and Other Assisters?” for more information).

State insurance laws and regulations vary by state, though commonly include:

Table summarizing state responsibilities for regulating private health insurance. Financial standards include insurer capital, reserve, and investment requirements, as well as state financial examinations. Market conduct oversight includes claims handling, underwriting, marketing, advertising, and investigations of unfair trade and claims practices. States regulate insurance policy forms by setting standards for contract provisions, terminology, and policy approval. States also determine certain coverage requirements and mandated benefits, resulting in variation in covered services across states. Premium regulation includes review of proposed rate increases and, in some cases, stricter premium-rating rules than federal law requires. Consumer protection responsibilities include handling complaints, enforcing consumer protections, and providing independent external review processes for certain coverage disputes.

Most states require health plans to provide specific data that is included in the state’s all-payer claims databases (APCDs). These are state databases that include medical, pharmacy, and often dental claims, as well as eligibility and provider files collected from and aggregated across all private and public payers in a state. APCDs can provide states with a perspective on cost, service utilization, and quality of health care services across the full spectrum of payers in a state, which can be a tool in state efforts to control health care costs and promote value-based care.

Some states are also developing additional state-level regulations related to health plan network adequacy, health plan price transparency, public option plans, reinsurance programs, and more. These state-level regulations and protections do not apply to enrollees in self-insured plans offered by private employers (see the section “What is Private Health Insurance” for more information). However, these enrollees may have some of these protections through other federal laws and regulations.

State legislatures enact state insurance laws and typically grant regulatory authority to the state’s insurance regulator/commissioner. State enforcement mechanisms vary widely by state, regulation, state resources, and staffing capacity. Shifting political priorities at the state level can also influence enforcement priorities and actions. For example, state insurance agencies may ensure compliance with certain benefit mandates by primarily relying on complaints from consumers, consumer advocates, or health care providers to trigger a compliance review of the plan in question, while other state insurance agencies conduct periodic systematic reviews of all plans subject to the law or regulation.

What Is the Role of Health Insurance Brokers and ACA Consumer Assistance Programs?

Copy link to What Is the Role of Health Insurance Brokers and ACA Consumer Assistance Programs?

Navigating an increasingly complicated health coverage landscape has increased the focus on the availability and expertise of entities that assist purchasers of health coverage (consumers and employers). Assisters can include agents and brokers who are paid commissions from insurers, as well as consumer assistance programs created by the ACA, which are often publicly funded and nonprofit, who may provide similar assistance as agents and brokers, but also specialize in individuals transitioning in and out of public programs such as Medicaid or assisting those without insurance to find coverage.

Agents and brokers have long played a significant role in connecting individuals and employers to private health coverage by helping them understand health insurance options and costs. An “agent” typically represents a single insurer and provides information about that insurer’s coverage options. A “broker” is not aligned with any one insurer but could, in theory, place coverage from any insurer selling products in a state.

Agents and brokers assist individuals in choosing a qualified health plan on a health insurance Marketplace. Their role in Marketplace enrollment has grown over the years. In the 2024 plan year, 78% of ACA coverage was sold through health insurance agents compared to 43% in 2016. Web brokers, who facilitate plan selection online through Marketplace capabilities, have also played a large role in Marketplace enrollment.

Agents and brokers in the health insurance Marketplace have faced scrutiny for alleged fraudulent activity in recent years due to consumer reports of unauthorized enrollment and plan switches by agents and brokers. In response, CMS, under President Biden, began requiring additional steps to be taken before agents and brokers can make changes to a consumer’s HealthCare.gov enrollment, and hundreds of agents’ and brokers’ Marketplace agreements were suspended for reasonable suspicion of fraudulent activity. In an attempt to address Marketplace fraud, the Trump administration finalized a regulation in 2025 that, along with the 2025 budget reconciliation law, creates new administrative hurdles for consumers to enroll in Marketplace coverage and receive premium tax credits. These 2025 actions made few changes to broker oversight requirements for Marketplace plans. The Trump administration also reinstated many agents and brokers suspended in recent years, and federal indictments related to broker fraud for actions that allegedly occurred as far back as 2018 still await resolution.

Even before the creation of the Marketplaces, agents and brokers had been selling coverage in the individual and group insurance market, especially to small employers needing expertise in finding health insurance for their employees. Large employers also use agents and brokers, who often work for employee benefit consultants or brokerage firms and receive commissions (or, in some cases, a fixed fee) to find vendors to support their self-insured group health plan or for placing other forms of insurance that they provide or make available to employees as “voluntary” benefits.

Broker Compensation Reporting. Employer plans governed by ERISA must meet ERISA fiduciary standards. These standards prohibit plans from contracting with a “party-in-interest,” which is an entity that may have a conflict of interest because it is receiving compensation from a third party for activity it is doing for the employer plan. For instance, a benefits consultant may be helping an employer find a third-party administrator (TPA) for its group health plan, and the consultant is paid by the employer for their work but also gets a commission from the TPA if the employer decides to use its services. Employers are prohibited from entering into this type of transaction with the consultant unless they can show it was done in a “reasonable manner.”

Under rules added to ERISA by the CAA, one way an employer plan can demonstrate that its contract with a broker/consultant is reasonable is to show that it received information from the broker/consultant about the compensation the broker/consultant received from the TPA. Under these rules, an employer plan fiduciary violates ERISA if it does not receive from a broker or consultant information about the direct and indirect compensation the broker receives. Also, insurers offering individual insurance (on- and off-Marketplace) and those offering short-term limited-duration plans must disclose to enrollees and report to CMS any direct or indirect compensation they pay to agents and brokers for enrolling individuals in this coverage.

Consumer Assistance Programs. The ACA required the creation of other types of assisters to assist consumers with enrollment, plan selection, insurance problems, and, in some cases, post-enrollment support. These programs must provide impartial, no-cost help to consumers and cannot be affiliated with an insurance company.

Navigator programs, which are federally funded through grants, were created to raise public awareness and assist individuals in enrolling in qualified health plans as well as provide post-enrollment support. Navigators participate in trainings and are required to be knowledgeable in eligibility and enrollment rules and available QHP options, and maintain privacy and security standards. In 2025, CMS announced a 90% cut in Navigator funding, the largest funding cut since the program began. The current plan year funding of $100 million will be reduced to $10 million for 2026. These cuts come as enhanced Marketplace subsidies are set to expire at the end of 2025 and federal cuts to Medicaid begin to take effect in 2026, both of which could result in significant coverage losses.

Related assisters include Certified Application Counselors (CACs) who also assist consumers in resolving insurance issues and identifying the coverage option that best suits their needs. CACs, however, are not required to meet the same standards as Navigators or participate in all of the activities required of Navigators (e.g., providing post-enrollment assistance). In states using the federally-facilitated Marketplace (FFM), CACs are overseen by Certified Application Counselor Designated Organizations (CDOs), which are designated by CMS and include organizations such as community health centers, hospitals, and social services agencies. To serve as a CAC in an FFM state, the individual must be affiliated with a CDO and is typically a staff member or volunteer. CACs are not federally funded and instead rely primarily on outside non-profit organizations and foundations. 

The ACA also established Consumer Assistance Programs (CAPs) to assist consumers with insurance problems and identify their best options for health coverage. Unlike the Navigator program, which was specifically created to assist Marketplace, Medicaid, and CHIP consumers, CAP programs also assist consumers with employer-sponsored coverage and other types of coverage. The ACA provided an initial appropriation for CAPs, which 35 states and Washington, D.C., took advantage of, but CAP programs have received no federal funding since 2012. Many states have continued their CAP programs using their own funds, but others have discontinued their operations.

What is the Future Outlook for the Regulation of Health Insurance?

Copy link to What is the Future Outlook for the Regulation of Health Insurance?

2025 and beyond will likely see a retrenchment in regulation at the federal level that could impact the private coverage gains of the last decade. While states will still play a significant role in regulating private health insurance, the fragmented structure of private health care regulation and enforcement means that states alone are limited in what they can do to affect national change or influence private employer-based coverage, where most insured Americans under 65 get their coverage. The future regulatory outlook for private health coverage will be shaped by the following three key features:

Deregulation and Litigation. The Trump administration has put in motion, through several executive orders and other actions, deregulation across the health care sector. For example, a January 2025 executive order required that for every new regulation promulgated, federal agencies must identify at least ten existing regulations to repeal, which could impede future rulemaking. Another executive order required all federal agencies to coordinate with the president’s Department of Government Efficiency (DOGE) to review all regulations to make sure they are consistent with “law and Administration policy.” Using this executive order, the Trump administration has limited the enforcement of final regulations on mental health parity and short-term, limited-duration plans. Also in February 2025, President Trump issued an executive order that rescinded several executive orders issued by President Biden, including one aimed at strengthening the ACA.

These types of regulatory rescissions and a general deregulatory executive agenda, along with disruptions in agency structure and the personnel layoffs in the federal health care agencies, could have long-term impacts on private health care regulation. The outcome of court challenges to many of these deregulatory actions will determine future developments. In addition, changes in how courts review agency decisions—that is, the major decisions by the Supreme Court to limit agency discretion—could be a barrier to the Trump administration’s deregulation initiatives, as federal courts now have more power to second-guess policy decisions of the President. Look for attempts at codifying the Trump administration’s priorities through congressional action to get past any court barriers. Also, expect to see more actions from this administration through executive orders, voluntary industry agreements, and sub-regulatory guidance (e.g., advisory opinions that approve various industry arrangements). Changing enforcement priorities for federal agencies could leave patients looking to state and private mechanisms to get the protections written in federal law.

Technology Advancements. Expect wide-ranging recommendations from major stakeholders on which aspects of artificial intelligence (AI) and telehealth should be promoted and protected from federal regulation. The Trump administration has already announced its plans to speed up the development of AI and reduce regulation. With limited federal regulation anticipated during this administration, much of the future outlook for consumer protections will depend on the voluntary actions of industry and how transparent those activities are. For example, in July 2025, the Trump administration announced a new voluntary initiative aimed at enhancing health data interchange (known as “interoperability”) and expanding patients’ access to their own health data and reported that more than 60 companies had pledged to participate. Open questions about data privacy, security, and accuracy are key concerns as the details of this initiative and new apps are developed. Participation is optional, and the initiative does not create any new legally binding requirements for these companies. While the market for digital health care tools could benefit from the emphasis on AI and virtual care, without updated federal privacy and security rules, such as HIPAA, and nondiscrimination requirements, consumers may have to look to state regulation for these protections. Additionally, new, expensive gene therapies and blockbuster medications will likely increase the overall cost of health care and could also challenge policymakers to rethink existing reimbursement structures and government intervention in pricing.

Consumer Choice. Look for policy shifts from consumer assistance and protection to efforts to broaden the health coverage choices available to consumers to include those that may not meet all of the ACA’s consumer protection requirements. The emphasis on “choice” will likely include efforts to encourage consumers to use tax-advantaged accounts such as health savings accounts, which can be used to set aside funds to purchase an increasing variety of items and pay for health care services provided via direct primary care arrangements and telehealth before the deductible applies. Policy debates on whether low-income individuals and those with chronic illnesses are best served by these account-based models are also possible.

Resources

Copy link to Resources

Citation

Copy link to Citation

Pestaina, K., Wallace, R., & Long, M., The Regulation of Private Health Insurance. In Altman, Drew (Editor), Health Policy 101, (KFF, October 2025) https://www.kff.org/health-policy-101-the-regulation-of-private-health-insurance/ (date accessed).