5 Questions and Answers About Medicaid and Provider Taxes

Published: Aug 20, 2026

The 2025 reconciliation law imposes significant new restrictions on states’ ability to generate Medicaid provider tax revenue, including prohibiting all states from establishing new provider taxes or from increasing existing taxes as well as reducing existing provider taxes for states that have adopted the Affordable Care Act (ACA) Medicaid expansion. Medicaid is jointly financed by the federal government and the states, with the federal government guaranteeing states federal matching payments with no pre-set limit. In federal fiscal year (FFY) 2024, the federal government paid 65% and states paid 35% of total Medicaid costs. States are permitted to finance the non-federal share of Medicaid spending through multiple sources, including state general funds, health-care related taxes (referred to as “provider taxes” throughout this brief), and local government funds.

Changes to provider tax rules will have significant effects on state budgets and may make it difficult for states to maintain current Medicaid spending without increasing state general fund spending; but could increase transparency around Medicaid financing. The changes come at a time when states are already experiencing overall slower revenue growth, and it is unclear how states will be able to make up the lost revenues. The changes could exacerbate existing state budget challenges and result in lower provider payment rates or reductions in Medicaid benefits or coverage, although the effects will vary by state.

This issue brief uses data from KFF’s 2025-2026 survey of Medicaid directors and from a proposed rule on provider taxes to describe states’ current provider taxes, explore how rules governing provider taxes are changing because of the 2025 reconciliation law and the regulations implementing that law, and summarizes which changes may affect each state.

1.How have states used provider taxes to help finance the state share of Medicaid?   

KFF’s 2025 Medicaid Budget Survey found that the majority of state Medicaid spending came from general fund revenues, but provider taxes contributed 18%. States have considerable flexibility in determining how to finance the state (or non-federal) share of Medicaid payments, within certain limits. Across all states, most of the state share of Medicaid spending comes from state general funds, but there is considerable variation in how much states rely on other funding sources. KFF’s 2025 Medicaid budget survey found that general funds accounted for a median of 70% of the non-federal share in state fiscal year (FY) 2026 enacted budgets, while provider taxes accounted for 18%, and funds from local governments or other sources accounted for 6% (this is relatively similar to 2018 data on non-federal share funding sources reported by the Government Accountability Office (GAO) and 2024 data on general fund spending from the National Association of State Budget Officers (NASBO)). 

All states but Alaska finance part of the state share of Medicaid funding through at least one provider tax and 41 states have three or more provider taxes in place (Figure 1). Medicaid provider taxes are defined as those for which at least 85% of the tax burden falls on health care items or services or entities that provide or pay for health care items or services (see Social Security Act, Section 1903(w)(3)(A)). Provider taxes may be imposed as a percentage of provider revenues or using an alternative formula such as a flat tax on the number of facility beds or inpatient days. States use provider tax revenues to fund Medicaid “base” rates and supplemental payments; to finance eligibility expansions, including the ACA Medicaid expansion; or to more generally support the Medicaid program. Over time, states have increased their reliance on provider taxes, with expansions often driven by economic downturns or a desire to fund eligibility expansions or provider reimbursement increases. Beyond helping finance the state share of Medicaid, permissible tax arrangements may have potential financial benefits for providers who are subject to the tax and serve a high volume of Medicaid patients.
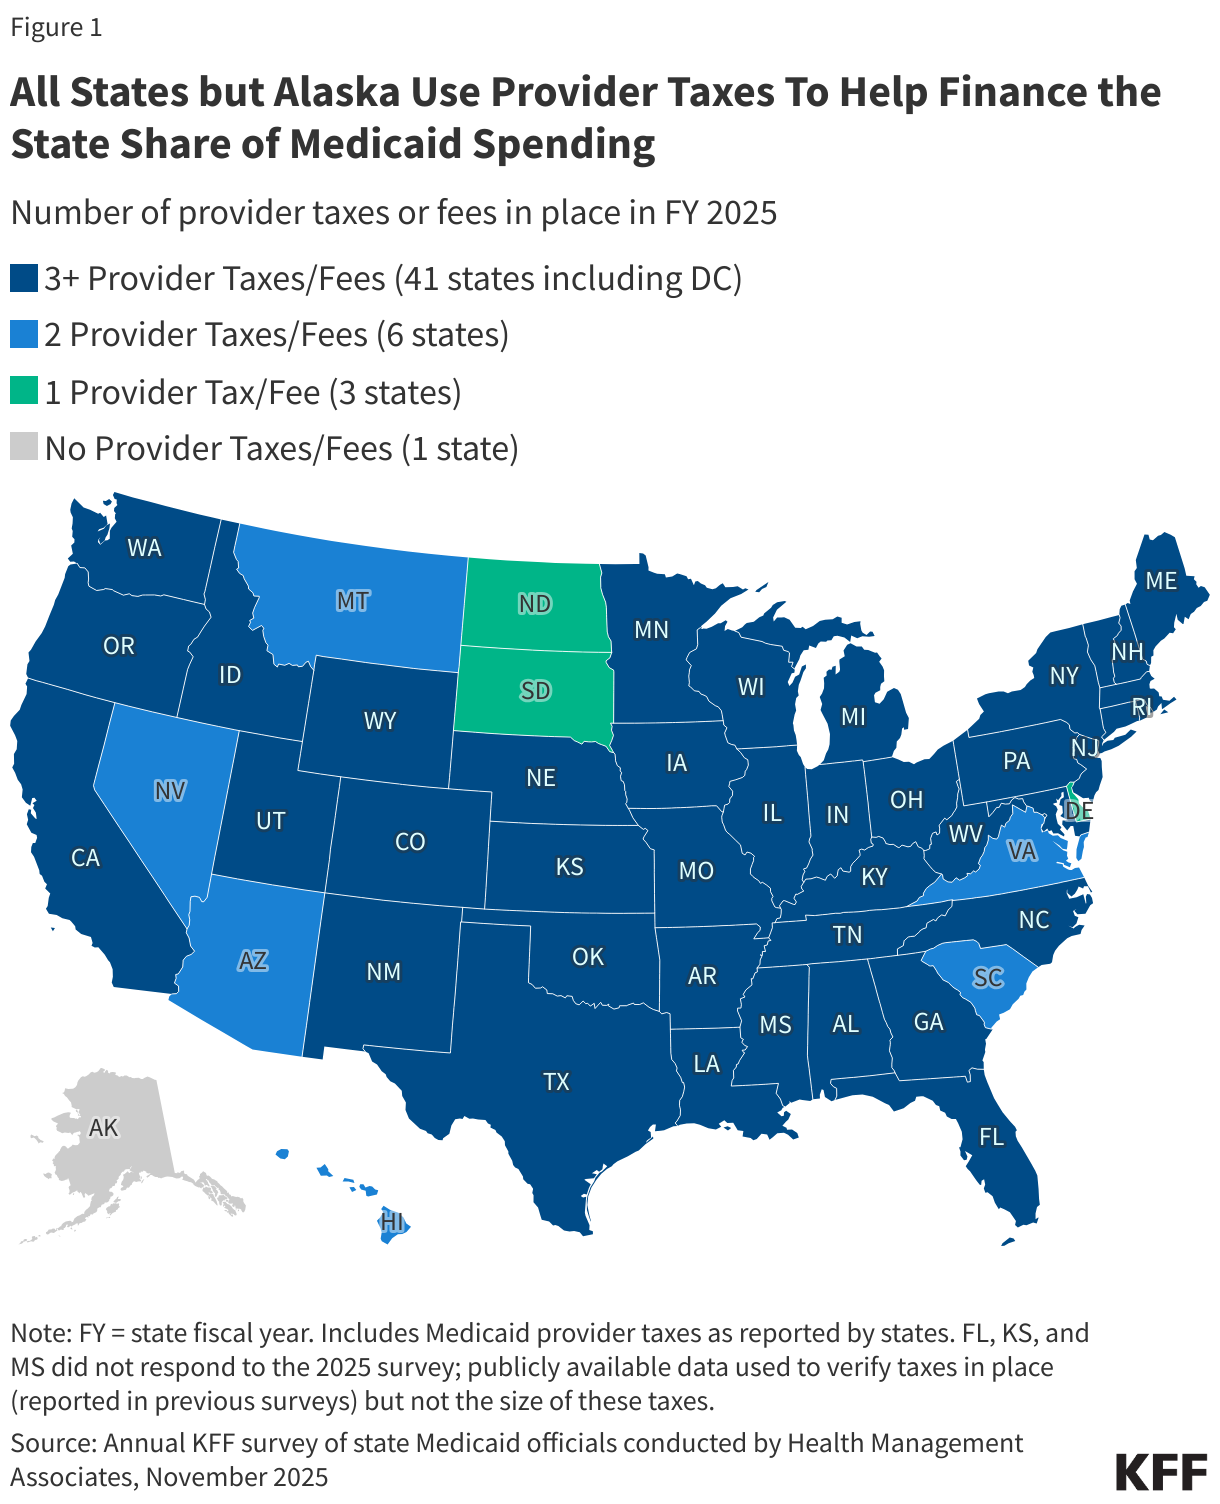
All States but Alaska Use Provider Taxes To Help Finance the State Share of Medicaid Spending (Choropleth map)

Provider taxes are most common for institutional providers. That includes hospitals (47 states), nursing facilities (45 states), and intermediate care facilities for people with intellectual or developmental disabilities (33 states, Figure 2). Provider tax revenues often finance supplemental payments to institutional providers, which may be a major source of revenues for those providers. Payment policies vary considerably by state, and research has shown that Medicaid base payment rates are below those of Medicare and often below hospitals or nursing facilities’ costs of providing services to Medicaid enrollees, causing some states to rely more heavily on supplemental payments than others to help cover costs. Beyond institutional providers, states have taxes on managed care organizations (MCOs) (22 states), ambulance providers (21 states), and “other” provider types (9 states) such as ambulatory care facilities and home care providers. Provider tax revenues are most likely to be near the 6% safe harbor limit (described in more detail below) for nursing facilities followed by hospitals and intermediate care facilities for people with intellectual or developmental disabilities (Figure 2).
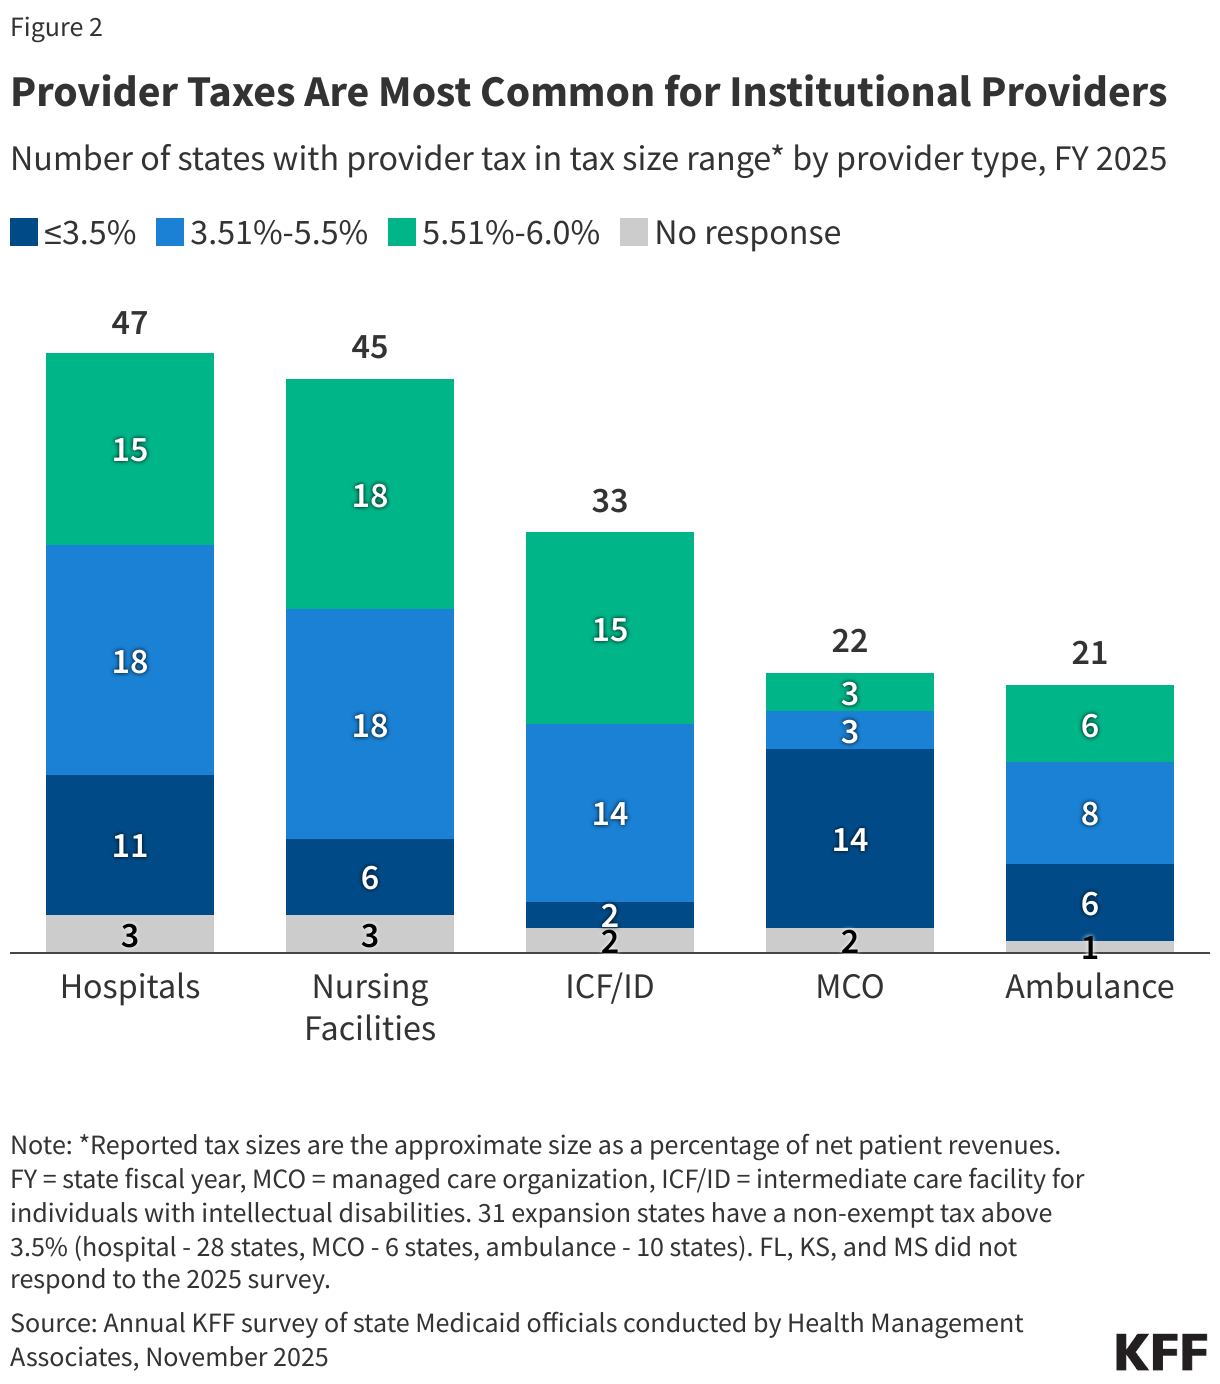
Provider Taxes Are Most Common for Institutional Providers (Stacked column chart)

CMS estimates that states will collect nearly $100 billion in provider tax revenues in 2026, mostly from hospital taxes (Figure 3). Historically, the federal government did not provide consistent or comprehensive publicly available data about states’ provider tax policies or revenue collections. In June 2024, the Medicaid and CHIP Payment and Access Commission (MACPAC), called for increased transparency over how states financed the non-federal share of Medicaid payments. However, CMS requested additional data from states about their provider taxes in 2025 and 2026. Using those data and their own projections, CMS estimates that tax revenues in calendar year 2026 will be $98.6 billion, with $61.8 billion coming from taxes on hospitals and $28.1 billion coming from taxes on managed care organizations.
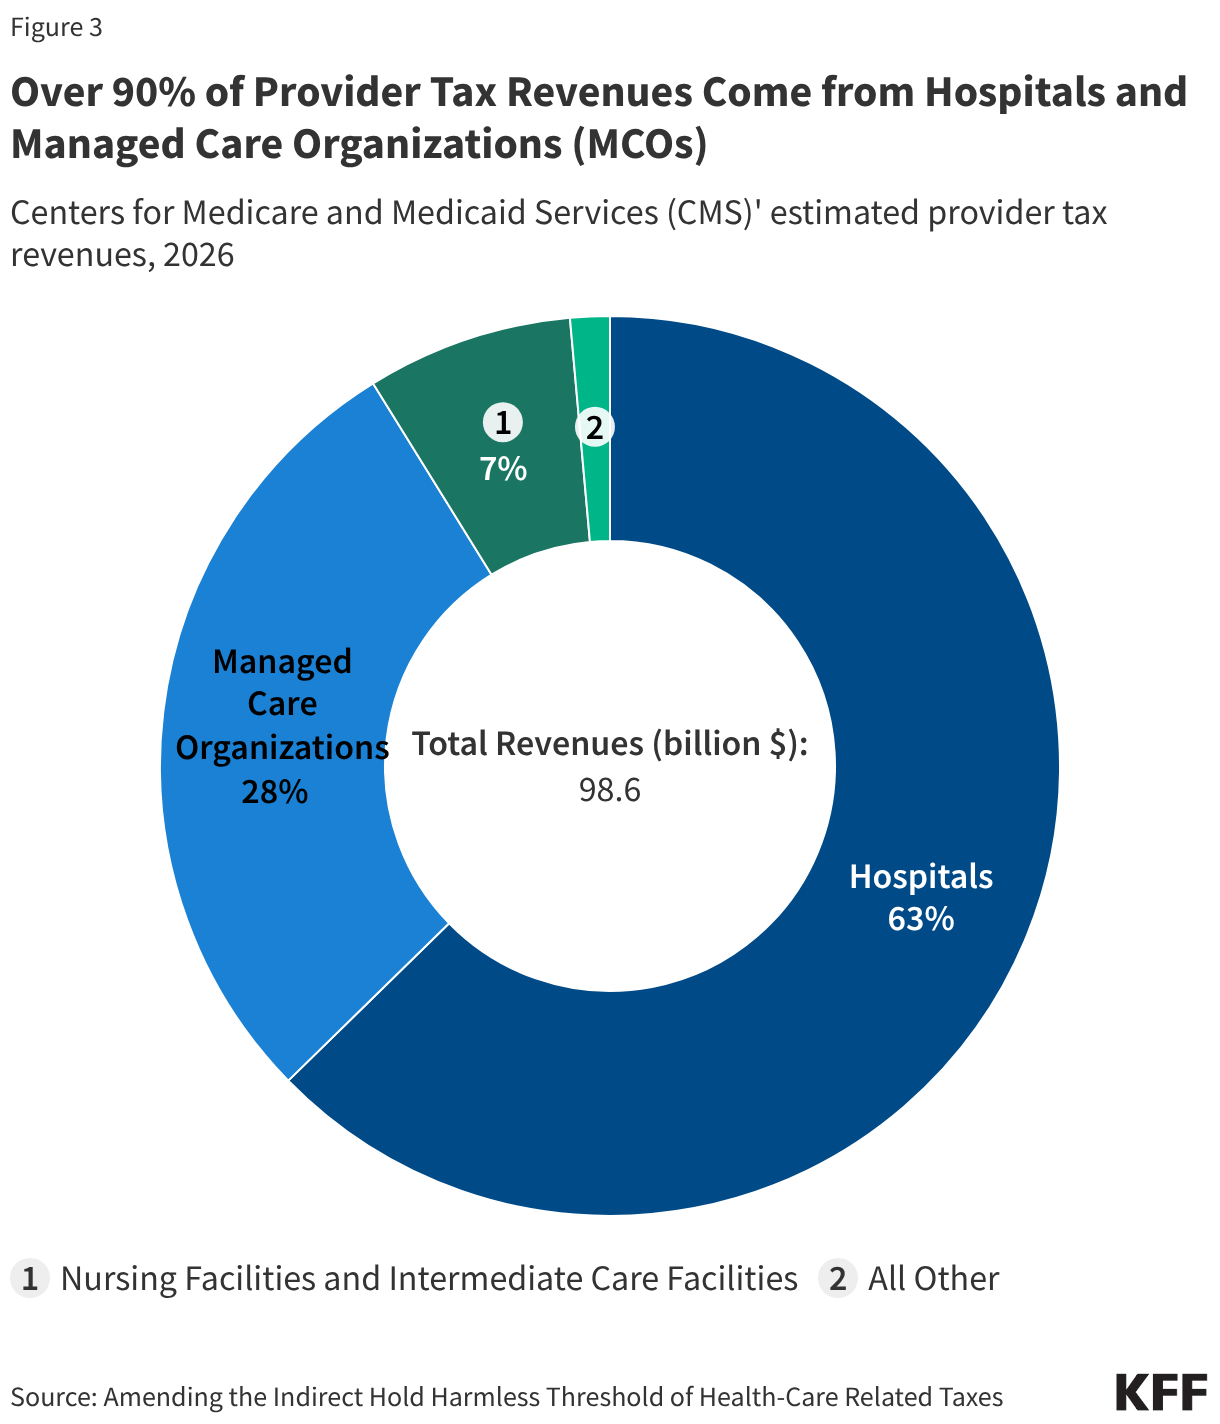
Over 90% of Provider Tax Revenues Come from Hospitals and Managed Care Organizations (MCOs) (Donut Chart)

2. What federal rules governed provider taxes before the 2025 reconciliation law?

Since the 1990s, federal rules governing provider taxes have included three core components—requiring taxes to be “broad-based,” “uniform,” and not hold providers “harmless.” Provider taxes were established in the 1980s, but particularly aggressive use of provider taxes following their establishment in the 1980s led to statutory and regulatory limitations beginning in the 1990s. Federal rules prior to passage of the 2025 reconciliation law specified that provider taxes must be:

  • Broad-based, which means the tax is imposed on all providers within a specified class of providers (e.g., the tax cannot be imposed only on providers that see primarily Medicaid patients);
  • Uniform, which means the tax must apply equally to all providers within the specified class (e.g., the tax rate cannot be higher on Medicaid revenue than non-Medicaid revenue); and
  • Not hold taxpayers (providers) “harmless,” which means states are prohibited from directly or indirectly guaranteeing that providers will receive their tax costs back (i.e., be “held harmless”).

To ensure tax programs are “broad-based,” CMS has specified 19 classes of providers (see 42 CFR Section 433.56). States may obtain “uniformity waivers” of the requirements that taxes be broad-based and uniform if the state can prove the net effect of the tax is “generally redistributive,” and the amount of tax is not directly related to Medicaid payments. In assessing whether provider taxes comply with federal laws, regulations specify that the hold harmless requirement does not apply when the tax revenues comprise 6% or less of net patient revenues from treating patients (see 42 CFR Section 433.68), a level sometimes referred to as a “safe harbor” or “hold harmless” limit.

Changes in the 2025 Reconciliation Law

The 2025 reconciliation law, signed by President Trump on July 4, 2025, imposes significant new restrictions on states’ ability to generate Medicaid provider tax revenue. The Congressional Budget Office (CBO) estimated provider tax policy changes from the 2025 reconciliation law would reduce federal Medicaid spending by $226 billion between 2025 and 2034. Those savings reflect the following changes to federal rules:

  • An effective prohibition on new provider taxes or increases to existing ones ($89 billion in savings). The law effectively prevents the enactment of any new provider taxes by establishing a hold harmless limit of 0% for any taxes that were not in effect as of July 4, 2025. It also prevents any increases to existing provider taxes, which are capped at their rates as of July 4, 2025.
  • Reduced limits on provider taxes in states that adopted the Affordable Care Act (ACA) Medicaid expansion ($102 billion in savings).  Beginning in FFY 2028, the law gradually reduces the hold harmless limit for states that have adopted the ACA expansion by 0.5% annually until the safe harbor limit reaches 3.5% in FFY 2032. The new limits apply to all provider taxes except for those levied on nursing facilities and intermediate care facilities.
  • Revisions to the conditions under which states may receive uniformity waivers ($35 billion in savings). Effective July 5, 2025, the law prohibits states from using uniformity waivers if the tax charges higher or lower rates based on the volume of Medicaid revenues or patients.

Changes in the July 2026 CMS Proposed Rule

CMS released a proposed rule in July 2026 to implement the hold harmless provisions in the 2025 reconciliation law, which included some provisions not required under the law. The list below highlights some of the key provisions included in the proposed rule:

  • Broader interpretation of taxes “in effect.” Under the proposed rule, CMS would recognize provider taxes as being in effect as of July 4, 2025 or earlier if they had been enacted. This is less restrictive than guidance issued in November 2025, which also required that all applicable uniformity waivers to have been approved by July 4, 2025 and for states to be “actively collecting” revenues as of July 4, 2025.
  • Establishing health insurers as a permissible class of providers. Although not required by the 2025 reconciliation law, the rule proposes to add a new “health insurer” provider class to expand CMS oversight of health-care related taxes that goes beyond the existing “MCO” provider class including Health Maintenance Organizations and Preferred Provider Organizations. The proposed rule does not define the new class, but CMS is seeking comments on the potential scope of the new provider class. Such taxes would be subject to all other requirements governing Medicaid provider taxes, including new limits in the 2025 reconciliation law. CMS notes that these taxes are often imposed through state insurance commissions or departments.
  • Discontinuation of the 75/75 test. The 2025 reconciliation law did not address the “75/75” test, under which taxes exceeding the hold harmless limit could remain permissible as long as more than 75% of taxpaying providers do not receive more than 75% of the cost of the tax back through enhanced Medicaid or other state payments. Starting in FFY 2027, the proposed rule would discontinue the 75/75 test.
  • Enhanced Reporting Requirements and Compliance System. The proposed rule would significantly expand state reporting requirements and introduce retrospective CMS review to determine ongoing state compliance with the new hold harmless limits. States would be required to submit data (interim in 2026 and final in 2028) to CMS to determine applicable hold harmless limits as of July 4, 2025. States would also be required to submit quarterly reports beginning October 1, 2026, supplying tax collection data as well as information on how tax revenues are used by the state and whether public providers are exempt from the tax.

Under the proposed rule, CMS estimates that federal Medicaid spending would decrease by $246 billion over the next ten years (2026- 2035). This is similar to the CBO estimates although the CBO estimate does not include effects for the year 2035, which accounted for $44 billion of CMS’ total federal spending reduction. While the difference in estimates is relatively small, there are a few key differences in the agencies’ assumptions:

  • States response. CBO assumed that states would replace 50% of the lost provider tax revenues with other funding sources but CMS assumes they will only replace 30%.
  • Coverage loss. CBO estimated that provider tax changes in the 2025 reconciliation law will increase the number of uninsured people by 1.2 million by 2034, but CMS estimates that there will be no enrollment loss associated with the loss of revenues. 

4. Which states may face reductions in existing provider tax revenues?

States that have adopted the ACA Medicaid expansion and have certain provider taxes above the new hold harmless limits will face reductions in existing provider tax revenues. KFF data show that an estimated 31 states will have to reduce one or more provider taxes on hospitals, MCOs, or ambulances because of the lower hold harmless limits in ACA expansion states (Figure 4). Additional states are likely to be affected because of taxes on other classes of providers. Hospital taxes are the most frequently affected, with 28 of the 31 affected states having a hospital tax over 3.5% of net patient revenues as of July 1, 2025. Over half of the Medicaid provisions in the 2025 reconciliation law apply only to ACA expansion states, including the lower hold harmless limits. Those changes—coupled with lower provider tax revenues—may make it particularly difficult for ACA expansion states to navigate a challenging fiscal climate and increasing numbers of uninsured residents.

If CMS’ proposed regulation is finalized with the new health insurer provider class, additional states will be affected, though it is unclear how many states currently have such taxes in place. CMS’ decision to establish health insurers as a provider class for the purposes of Medicaid provider tax rules means that additional taxes will be subject to new hold harmless limits and in ACA expansion states, additional taxes may be subject to the decreasing hold harmless limits over time.
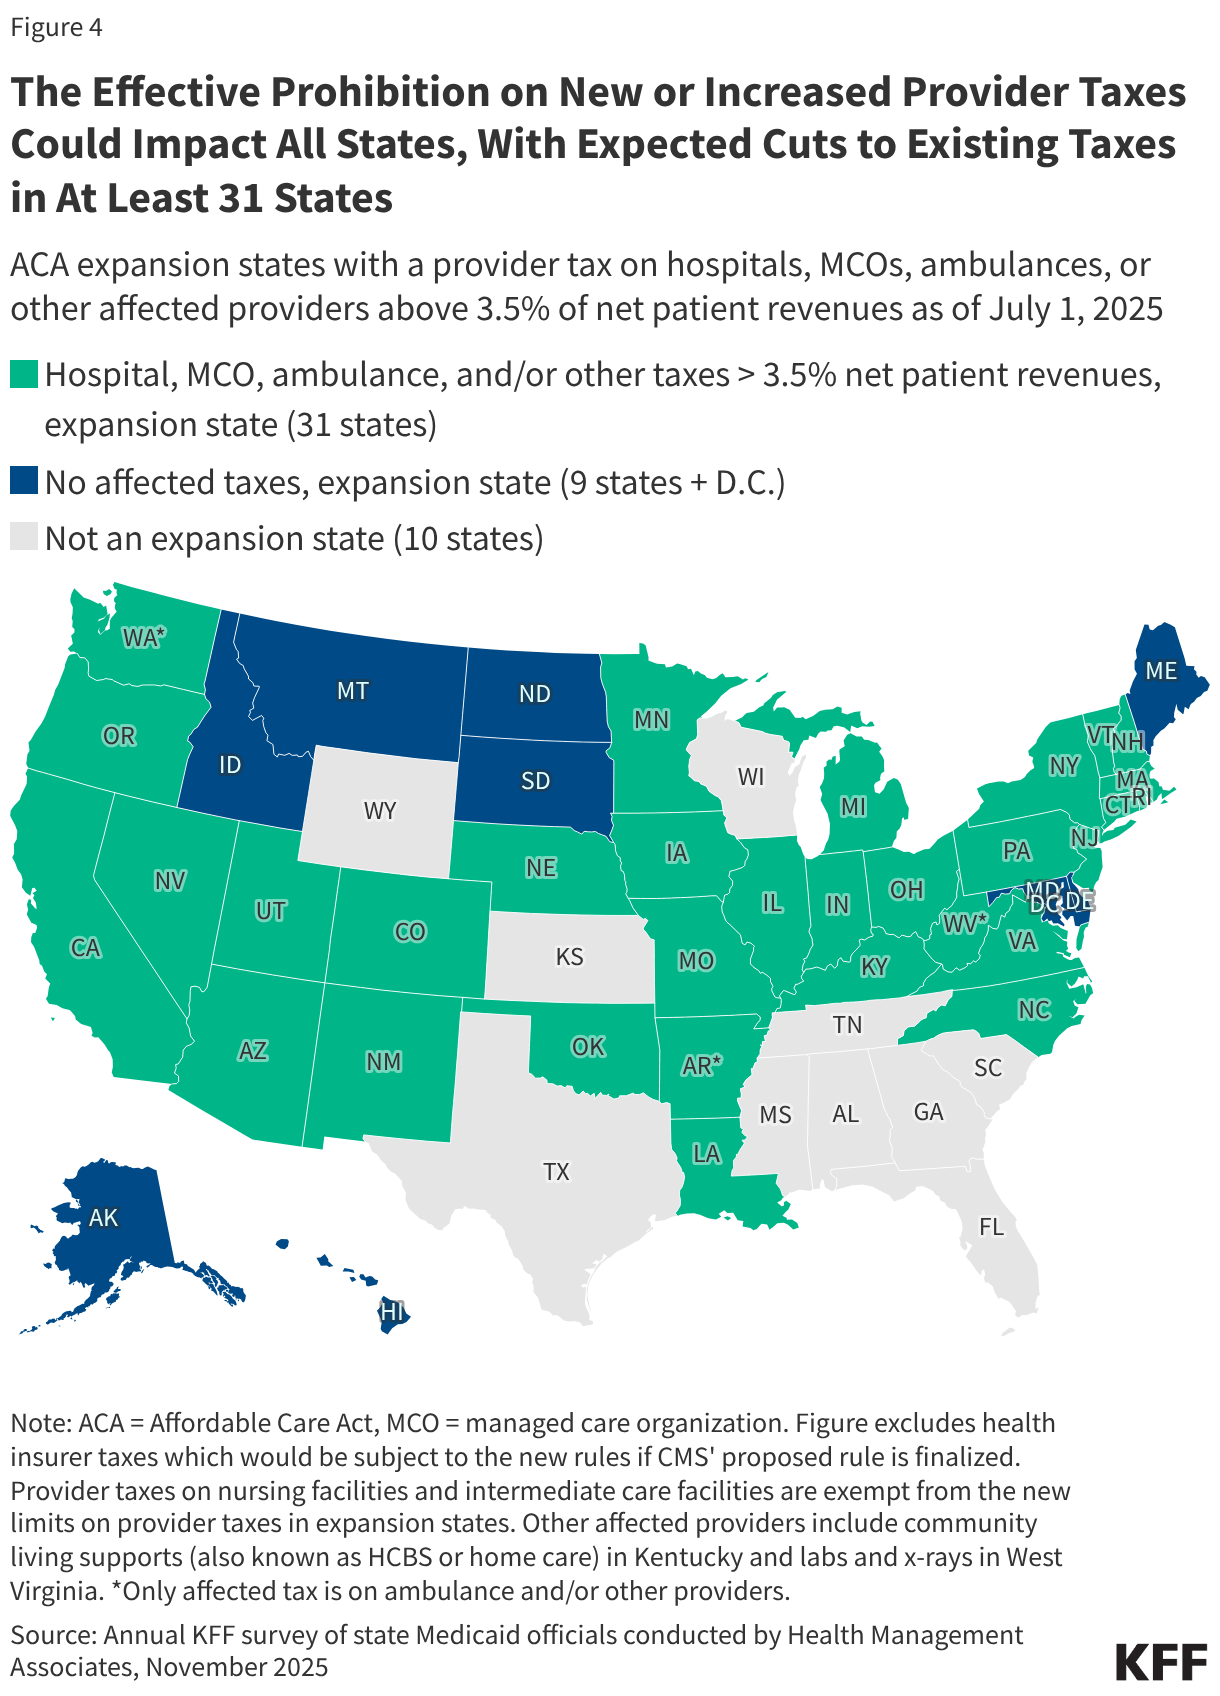
The Effective Prohibition on New or Increased Provider Taxes Could Impact All States, With Expected Cuts to Existing Taxes in At Least 31 States (Choropleth map)

5. Which states may need to rework their “uniformity waivers?”

Uniformity waivers have allowed states to waive the requirement that provider taxes be broad-based and uniform if CMS determines that the tax is “generally redistributive.”  Provider taxes established through such waivers have generally taxed some types of providers within a class more heavily than others. States may use uniformity waivers to achieve policy goals such as limiting tax burdens for sole community hospitals, rural hospitals, or other vulnerable providers; but states have also used the waivers to impose taxes primarily on Medicaid providers. The disproportionate taxation of Medicaid providers has raised CMS concerns, including during the Biden Administration, and in May 2025, the Trump Administration released a proposed rule that aimed to address those concerns. The final rule was published on February 2, 2026 (Box 2).

The 2025 reconciliation law prohibits states from using uniformity waivers if the tax charges higher or lower rates based on the volume of Medicaid revenues or patients. The law specifies that taxes may not be considered generally redistributive if the state effectively varies tax rates based on the providers’ Medicaid revenues or patients, even if the tax does not explicitly name “Medicaid” when establishing the tax rates. The requirement is largely targeted at MCO taxes but may also apply to other provider tax types. It is effective as of July 5, 2025, but the Secretary may give states up to three fiscal years to come into compliance. The final rule on uniformity waivers provides states with transition periods that depend on what type of tax the waiver applies to and the most recent date of CMS approval for the waiver. Specifically:

  • For taxes on MCOs with a waiver approval within 2 years of April 3, 2026, states have until the end of the current calendar to transition their taxes (this is expected to be the case in California and at least three other states).
  • For all other taxes on MCOs, states have until the end of FY 2027 (which in most states, means they would need to be complying by July 1, 2027).
  • For taxes on entities other than MCOs, states have through the end of FY 2028 to come into compliance.

States may come into compliance by either submitting a new waiver proposal that meets the new requirements from the final rule (Box 2) or they may otherwise modify their tax such that no waiver is necessary.

The final rule states that new limits on uniformity waivers will affect at least nine taxes in at least seven states, with effects starting as early as January 1, 2027 (Figure 5). CMS did not identify the specific states in the final rule, but in the proposed rule, CMS specifically named California, Massachusetts, Michigan, and New York as being affected.  KFF and other researchers expect that the other three states are Illinois, Ohio, and West Virginia. The final rule states that existing MCO taxes would now be prohibited in seven states unless the taxes were modified, and that within those seven states, there were at least two additional taxes affected, including one on hospitals and one on nursing homes. However, elsewhere, in the preamble to the final rule, CMS indicated that there were two nursing facility taxes that would now be prohibited. (It’s unclear whether the second nursing facility tax is within the seven states or in an eighth state.) CMS indicates that additional taxes may need to be modified or eliminated, but it is unknown which states have such taxes or what types of providers the taxes pertain to. Beyond uncertainty surrounding the scope of affected taxes, much remains unknown about how states may respond to the new rule.

Box 2: CMS’ Final Rule on Uniformity Waivers

Since 1993, CMS has assessed whether proposed taxes are “generally redistributive” using a statistical formula that assesses whether a state’s tax has a tendency to “derive revenues from taxes imposed on non-Medicaid services in a class and to use these revenues as the State’s share of Medicaid payments” (58 Fed. Reg. 43164, August 13, 1993). Consistent with Section 71117 of the 2025 reconciliation law, the February 2026  final rule prohibits all taxes that have differential tax rates based on Medicaid revenues or patients even if they meet the statistical test. The final rule focuses primarily on managed care organization (MCO) taxes and cited examples where nearly all tax revenues were paid by Medicaid MCOs with private health plans paying nearly none, but notes other types of taxes would also be affected.
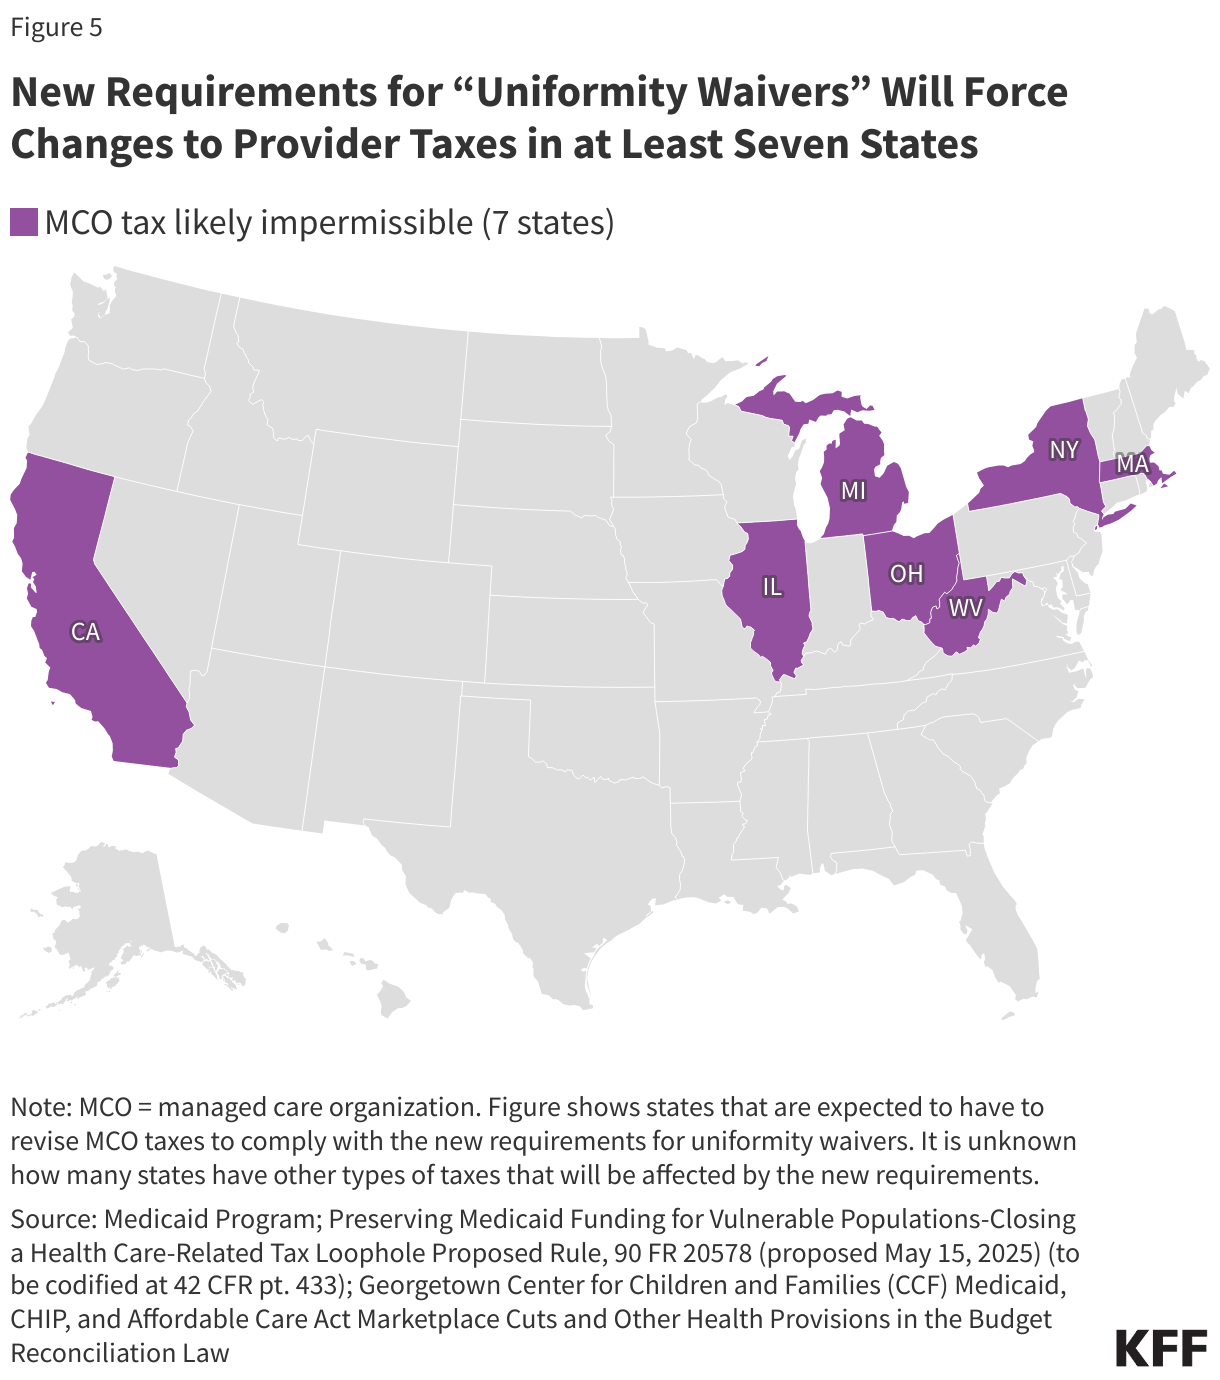
New Requirements for “Uniformity Waivers” Will Force Changes to Provider Taxes in at Least Seven States (Choropleth map)

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

Provider Taxes Not Exempt From the Reconciliation Law’s Reduction in the Safe Harbor Limit for ACA Expansion States (Table)

HHS Public Health Policy Actions Under the Trump Administration 2025-2026

Published: Aug 19, 2026

Note: Originally published on Nov. 12, 2025, this resource is updated as needed, most recently on August 12, 2026, to reflect additional developments. 

Since assuming office for a second term, President Trump and officials in his administration have instituted numerous policy actions through the Department of Health and Human Services (HHS) affecting public health in the U.S. This resource lists and briefly describes key actions in the order in which they were first issued, reported or announced, with subsequent linked actions and related outcomes also included with each entry. As new policy changes occur, they will be added. 

This resource is not meant to be exhaustive of all administration actions related to public health, as many other federal policy changes – including outside of HHS – have public health implications but are not captured here.

Additional KFF resources on administrative actions related to global health, LGBTQ+ health, and mental health and substance abuse are also available.

Date

|

Action/Description

January 20, 2025Presidential Executive Orders precipitate removal of some HHS websites and health data.
– In the first days of his second term President Trump issued a number of Executive Orders (EOs), including EOs that revoked many Biden administration orders and programs, and instituted new federal guidance related to “gender ideology,” “diversity, equity, and inclusion (DEI),” and “merit-based opportunities.” These EOs have implications for public health, particularly related to the collection and presentation of data and websites by the federal government. For example, in response to the EOs, HHS began to remove thousands of websites and numerous federal databases with public health information deemed to be related to DEI, LGBTQ, reproductive health, HIV/AIDS research, health disparities, and more, and limited some data collection and analysis in these areas. A lawsuit was filed to reverse these removals, and some information has been restored over time. In September, the administration agreed to restore all previously removed health-focused websites and data to versions that had existed on January 29, 2025.
February 7, 2025NIH announces change to indirect cost rate guidance.
– As part of grants for health research, the National Institutes of Health (NIH) provides “indirect cost” funding to grant recipients, which supports administration and facilities costs at grantee institutions. On February 7, NIH announced it would apply a new 15% “standard indirect cost rate” on all grants, which would apply to any new grants and to existing grants for expenses as of February 10, 2025. This was challenged in federal court and federal judges placed holds on the policy, first through a temporary restraining order affecting 22 states on February 10, a nationwide preliminary injunction on March 5, and a permanent injunction on April 4; prior rates still apply for the time being. The administration appealed the ruling and legal proceedings continue. If implemented, a 15% indirect cost rate would be a much lower rate compared to historical NIH rates and would amount to a significant cut in funding for institutions performing NIH-sponsored health research.
February 13, 2025Robert F. Kennedy, Jr. confirmed as HHS Secretary under President Trump.
– The Senate voted 52-48, along party lines, to confirm Robert F. Kennedy, Jr. as the Secretary of Health and Human Services.
February 13, 2025President Trump issues Executive Order (EO) establishing MAHA policy agenda and MAHA Commission.
– The EO outlines the purpose and objectives of the Trump administration’s Make American Healthy Again (MAHA) efforts. Stating that the U.S. must “re-direct our national focus…toward understanding and drastically lowering chronic disease rates and ending childhood chronic disease,” it directs federal agencies to “aggressively combat” mental health disorders, obesity, diabetes, and other conditions. It also establishes the MAHA Commission to advise the President, naming Secretary Kennedy as Chair. The EO directs the Commission to submit an assessment on how to combat the “childhood chronic disease crisis” within 100 days, and a strategy to address the crisis within 180 days, setting in motion processes to develop further public health strategies and plans (discussed in other entries below). 
February 14, 2025White House, DOGE initiate “reduction in force (RIF)”, including for HHS personnel.
– The EO outlines the purpose and objectives of the Trump administration’s Make American Healthy Again (MAHA) efforts. Stating that the U.S. must “re-direct our national focus…toward understanding and drastically lowering chronic disease rates and ending childhood chronic disease,” it directs federal agencies to “aggressively combat” mental health disorders, obesity, diabetes, and other conditions. It also establishes the MAHA Commission to advise the President, naming Secretary Kennedy as Chair. The EO directs the Commission to submit an assessment on how to combat the “childhood chronic disease crisis” within 100 days, and a strategy to address the crisis within 180 days, setting in motion processes to develop further public health strategies and plans (discussed in other entries below). 
February 14, 2025President Trump issues Executive Order prohibiting federal funding to schools and universities with COVID-19 vaccine requirements.
– The EO requires HHS to work with the Department of Education to prohibit COVID-19 mandates in schools, by issuing guidelines for compliance and barring federal funds from going to any educational agency, K-12 school, or institution of higher education that requires COVID-19 vaccination to attend in-person education programs (educational vaccine mandates are set at the state level). Educational vaccine requirements are set at the state and local levels. At the time the EO was released in February, no state required K-12 students to be vaccinated against COVID-19 while 15 colleges required Covid vaccines for students. However, by March 14, 2025 all of those colleges had ended their COVID-19 vaccine requirements for students.
February 18, 2025Secretary Kennedy announces public health policy priorities during HHS welcome ceremony.
– In his first remarks to HHS staff, Secretary Kennedy announces the public health priorities for his tenure. This include investigating the childhood vaccine schedule, tackling corruption and promoting transparency, and addressing a “chronic disease epidemic” especially in children, which he says may be linked to pesticides, food additives, antidepressants, microplastics, cellphone emissions, and other factors.
February 28, 2025Secretary Kennedy issues new rule ending public comment requirement for HHS grants and contracts.
– The new rule rescinds a prior HHS policy on “Public Participation in Rule Making” (the “Richardson Waiver,” dating back to 1971) and “re-aligns the Department’s rule-making procedures with the Administrative Procedure Act.”  As a result, “matters relating to agency management or personnel or to public property, loans, grants, benefits, or contracts” are exempt from the notice and comment procedures. This removes what had been a key step in the rulemaking process requiring public notification and a comment period. For example, changes to HHS policies related to work requirements for Medicaid and NIH funding would no longer require public comments under the new rule. This could streamline implementation of HHS policy, but also reduce public visibility on changes before they take effect.  Some lawmakers and public health focused groups have asked HHS to return to the prior requirements under the Richardson Waiver. 
March 7, 2025HHS announces that CDC will conduct a study of factors contributing to the rise in autism in the U.S.
– In statements to the press, HHS officials indicate CDC will initiate a study looking at the factors that are contributing to the rise in autism diagnoses in the U.S.. To date, no new CDC study results on this topic have been released though in a related development, in September 2025 President Trump and HHS leadership announced at a press conference and through a White House Fact Sheet that they believe there is a link between acetaminophen (e.g., Tylenol) use in pregnancy to autism (further details provided below). President Trump and Secretary Kennedy both have a history of linking vaccines and autism, even though there is no evidence of such a link.
March 13, 2025Food and Drug Administration (FDA) releases guidance on 2025-2026 influenza vaccine composition.
– The FDA guidance identifies which influenza virus strains manufacturers should use as components of 2025-2026 influenza vaccines. To develop these recommendations, FDA convened meetings of federal scientific and public health experts, including from FDA, CDC, and Department of Defense, but did not consult with the FDA’s Vaccines and Related Biological Products Advisory Committee (VRBPAC) or other professional groups outside the government. FDA had canceled the scheduled VRBPAC meeting on this topic, and the lack of input from outside experts was a break from past years’ practices. In addition, in past years there was active participation and coordination between U.S. federal experts and global technical experts working under the auspices of the World Health Organization (WHO), but official communications with WHO-linked experts has been curtailed since the Trump administration announced in January 2025 that the U.S. was withdrawing its membership from the UN agency.
March 17, 2025NIH initiates termination of numerous grants for HIV prevention and treatment programs.
– The canceled NIH grants include support for researchers investigating use of PrEP, medication used pre-exposure to prevent HIV infections, and programs focused on HIV/AIDS in adolescents and young adults. Even as the first Trump administration supported HIV/AIDS prevention and treatment efforts, including through a highly visible federal effort to “end the HIV epidemic” in the U.S. by 2030, these same programs have now been targeted for cuts (further details below).   
March 17, 2025HHS removes Surgeon General warning declaring gun violence a public health crisis.
– The HHS website was changed, removing a 2024 advisory from the Surgeon General on the public health impacts of gun violence. In addition to removing the Surgeon General’s warning, the administration has rolled back a number of gun safety policies in place during the Biden administration. The White House Office of Gun Violence Prevention, established during the Biden administration was shut down in early 2025. Further, significant numbers of staff at CDC’s Injury Center, which collects data on violent deaths and injuries, and CDC’s Division of Violence Prevention have been let go as part of the Trump administration’s reduction in force efforts.
March 25, 2025HHS and CDC seek to pull back $11 billion in supplemental COVID-19 and public health funding from state and local health departments.
– In a statement, HHS says it intends to pull back $11.4 billion in supplemental funding that had been provided by Congress for state and local public health departments through CDC for pandemic response activities. Following the announcement, on April 1, a group of 23 mostly Democratic-led states sued the Trump administration over the attempt to pull back this funding.  On April 3, a federal judge placed a temporary block on the administration’s actions, and on May 16, another federal judge indefinitely blocked the administration from enacting its funding pull back for the states that are part of the lawsuit. As of late August 2025, almost 80% of the funds initially targeted for cuts by the Trump administration had been restored for the 23 states that won in court. However, funding has not been restored to the remaining states, the majority of which are Republican-led.
March 27, 2025HHS announces a major re-organization and job cuts plan.
– HHS announces plans for a major restructuring of the department, in accordance with President Trump’s February 26 EO on “Implementing the President’s ‘Department of Government Efficiency’ Workforce Optimization Initiative.” The announcement says HHS will create an Administration for a Healthy America (AHA), which would combine several existing HHS offices including the Office of the Assistant Secretary of Health (OASH, which contains the Surgeon General’s Office), the Health Research and Services Administration (HRSA), the Substance Abuse and Mental Health Services Administration (SAMSHA), the Agency for Toxic Substance and Disease Registry (ATSDR), and the National Institute for Occupational Safety and Health (NIOSH). In addition, the Administration for Strategic Preparedness and Response (ASPR) at HHS would be moved under CDC. The announcement also says HHS will reduce its workforce by eliminating 10,000 full-time positions. Combined with other reduction in force efforts, a total of 20,000 HHS workers are expected to lose their jobs.

On May 5, a coalition of 19 Democratic-led states and the District of Columbia filed a lawsuit against the mass firing of federal health workers and re-organization of HHS. On May 10, a court ordered a temporary pause on sweeping federal firings at HHS and other agencies. On July 1, a federal judge blocked mass firings at HHS, saying they are likely unlawful. However, on July 8 the Supreme Court overturned the lower court decisions, allowing the Trump administration to proceed with job cuts. As of August it is estimated that over 20,000 jobs at HHS have already been cut, meaning the administration already met its initial workforce reduction goal.

Regarding re-organization, some organizational changes have been implemented at HHS, with major cuts or closures to public health related offices such as the HHS Office of Infectious Diseases & HIV Policy, the HHS Office of Minority Health, and HRSA’s Bureau of Primary Health Care.  However, other proposals such as the formation of an Administration for a Healthy America (AHA), have not yet been implemented. Implementing AHA to the extent proposed is likely to require approval from Congress, though so far Congress has not acted on legislation codifying these proposals.
March 31, 2025HHS withholds portion of Title X family planning service grants. 
– HHS notifies one in five current grantees of the federal Title X family planning program that a portion of their funding would be temporarily withheld. This funding freeze affects all nine Planned Parenthood grantees, in addition to 7 other nonprofit grantees, and it is estimated that a total of 879 clinics (24% of all Title X clinics) in 23 states are affected. After several months, funds were reinstated to some organizations, but the Planned Parenthood grantees have still not had their funding reinstated.
April 1, 2025HHS ends federal support for the “Safe to Sleep” program, which focuses on prevention of infant deaths during sleep.
– The Trump Administration ends federal participation in Safe to Sleep, a national campaign that focused on educating parents of newborns about safer sleeping practices for infants that can prevent death. The program, supported through the NIH’s National Institute of Child Health and Human Development (NICHD) Office of Communications in recent years, had been in existence for over 30 years and had contributed to a major decline in sudden infant deaths. The NICHD office was eliminated on April 1, along with federal support for “Safe to Sleep.”
April 2, 2025HHS requires CDC to reduce contract spending by $2.9 billion as part of DOGE cost reduction efforts.
– According to reports, HHS orders CDC to reduce its contract spending by $2.9 billion by April 18.CDC contract funding has been used to support several services at the agency including security, cleaning, and computers/technology. The sudden requirement to cut this spending by approximately 35% affects CDC operations. 
April 7, 2025HHS Secretary Kennedy announces changes to fluoride policies.
– Secretary Kennedy announces a plan to implement a number of changes to federal policy related to water fluoridation, including stating that CDC will stop recommending water fluoridation as a public health intervention (though to date, HHS and CDC still recommend community water fluoridation). In addition, Kennedy says the defunct Community Preventive Services Task will be revived and reconvened, with a goal of studying and making recommendations about water fluoridation. Kennedy also called on states to ban fluoride in their drinking water. Already this year Utah and Florida have banned community water fluoridation, the first states ever to do so.
April 17, 2025FDA informs Pfizer/Moderna that mRNA COVID vaccines will require an expanded warning label about myocarditis.
– In letters sent April 17, the FDA informs Pfizer and Moderna they must alter the warning labels for their COVID-19 mRNA vaccines to include expanded risks for myocarditis and pericarditis. Previously, the warning labels for these vaccines noted risks for these conditions for those aged 18 to 24 years (Moderna) and 12 to 17 years (Pfizer). However, updated labels are required to include new language saying “the observed risk of myocarditis and pericarditis following vaccination with mRNA COVID-19 vaccines has been highest in males 12 through 24 years of age” and that “persistence of abnormal cardiac magnetic resonance imaging (CMR) findings that are a marker for myocardial injury was common.”  According to FDA, the labels must also include more information about these conditions and their health risks.  Since the letters were sent, the companies have complied with the new FDA requirements. FDA approved the updated label language on June 25.
April 22, 2025FDA and HHS announce measures to phase out use of petroleum-based food dyes.
– FDA and HHS announce a series of steps the federal government will take to remove petroleum-based synthetic dyes from the U.S. food supply. These actions include initiating a process to revoke federal authorization for two such dyes and planning phase-outs by the food industry for others. In addition, the government will support research on food additives and children’s health and authorize natural alternative coloring options. Under the current plan, the phase-outs will occur through voluntary action taken by food companies.
May 1, 2025HHS announces a $500 million investment in a “next generation universal vaccine platform.”
– HHS and NIH announce that $500 million in funding will be directed to a new effort  to develop a “universal vaccine platform for pandemic-prone viruses.” The platform uses inactivated whole viruses, and is part of a broader federal effort to develop universal vaccines called “Generation Gold Standard.” The funds for this new investment appear to be re-purposed vaccine development funds from the Biden Administration’s NextGen initiative to develop next generation COVID-19 vaccines.
May 2, 2025White House Releases FY 2026 President’s Budget Request calling for major fundings cuts at HHS.
– The White House released an outline of the administration’s budget request for FY2026 and on May 30, the White House submitted the full Budget Request for FY2026 to Congress. The request proposes steep cuts to the HHS budget, including cuts for CDC, HRSA, SAMHSA, NIH, eliminating the Hospital Preparedness Program at ASPR, and reducing funding and cutting some programs focused on HIV/AIDS research and response. The budget request also asks Congress for $500 million to support a new “Administration for a Healthy America (AHA)” and MAHA-related priorities. The President’s Budget Request is only a proposal, as it is Congress that ultimately decides how much money the federal government appropriates. So far, Congressional spending bills for FY2026 have not included cuts to HHS of the magnitude requested by the President, and Congress has not provided the requested $500 million for AHA though budget negotiations continue.   
May 5, 2025White House Executive Order restricts funding and increases oversight for “gain of function” research at HHS.
– In an EO titled “Improving the Safety and Security of Biological Research” the White House cites concerns with federally funded “gain-of-function” (GOF) research on biological agents and states the Biden administration allowed dangerous GOF research to occur without sufficient oversight. The EO directs the Secretary of HHS to coordinate with other relevant Executive branch offices to establish guidance to end federal funding of “foreign entities” where GOF is being undertaken or in countries lacking oversight of GOF research. The EO requires the relevant Executive offices to submit updated policies and guidance for all federally supported GOF-related research, and to develop a strategy for managing risks of non- federally funded GOF research. The full implications of the EO are not yet clear, as the Executive branch offices must develop and implement specific guidance and regulations. According to outside experts, potential benefits of the EO include more transparency and stricter enforcement of dangerous research, while potential risks include hindering beneficial research that is not GOF and researchers choosing to curtail beneficial research to avoid potential repercussions under evolving federal restrictions.
May 20, 2025FDA leaders announce clinical trials will be needed for approval of certain new COVID vaccine formulations.
– In a medical journal article, FDA leaders indicate that going forward, for federal approval of new or updated COVID-19 vaccines (“boosters”) for use in individuals who are not considered at higher risk (defined as persons 65 or older or those with certain health conditions), will require vaccine makers to present evidence from randomized, placebo-controlled trials that demonstrate safety and efficacy. The announced policy is a departure from prior years when FDA did not require new trial data to authorize or approve boosters, but instead allowed approvals based on immune response evidence. The new policy could hinder investments by pharmaceutical companies in developing new COVID vaccine formulations, given the greater expense and time required to conduct new, full clinical trials.
May 22, 2025MAHA Commission Report on childhood chronic disease published.
– The first official report from the MAHA Commission (established by the February 13 EO discussed above) discusses factors contributing to a “chronic disease crisis” for U.S. children and provides a “call to action”. The report highlights four main drivers of the crisis: poor diet (primarily due to consumption of ultra-processed foods), exposure to chemicals, lack of physical activity and chronic stress, and “overmedicalization (excessive use of prescription drugs, such as antidepressants). The report calls for federal agencies to “close critical research gaps and guide efforts to better combat” these issues. It also says the MAHA Commission will develop and release a strategy in August (discussed below). The report expanded on the ideas initially outlined in the February EO and provided more details on Secretary Kennedy’s priorities to address chronic disease in children. There was some criticism of the report after its publication, with experts questioning some of the evidence and conclusions and pointing out significant errors and studies cited that did not exist, which indicated that artificial intelligence was likely used to help write the report. 
May 23, 2025Administration ends NIH funding for several HIV vaccine research projects. 
– NIH notifies two grant recipients working on broadly neutralizing antibody research for HIV vaccines of the cancelation of their funding.  The canceled grants supported early-stage vaccine development research that uses a different approach than other HIV vaccine candidates. Some other HIV vaccine candidates remain in the development pipeline and clinical trials continue, but the absence of this early-stage research could jeopardize the development of additional candidates going forward.
May 27, 2025HHS Secretary Kennedy announces CDC will no longer recommend COVID vaccines for healthy pregnant women and children.
– In a video post on X, Secretary Kennedy announces “the COVID vaccine for healthy children and healthy pregnant women has been removed from the CDC recommended immunization schedule.” The announcement was a departure from the typical process for changing vaccine recommendations, which includes review and input from the Advisory Committee on Immunization Practices (ACIP) and a notification from the CDC Director. Initially, the implications of changing CDC guidance without ACIP input were unclear given that no-cost insurance coverage for vaccination is linked to ACIP and CDC recommendations. On May 30, CDC changed the language on its website for COVID-19 vaccines, removing its prior recommendation for pregnant women to be routinely vaccinated and stating that healthy children 6 months to 17 years old could be vaccinated in consultation with health care providers/parents – a recommendation known as “shared decision-making,” which would mean insurance would still have to cover such vaccinations. On July 7, a coalition of professional medical organizations filed a lawsuit against HHS over the new COVID-19 vaccine recommendations, saying the department did not follow federal procedures in making the change and also mislead the public on the issue (on January 6, 2026, a federal court confirmed these plaintiffs have standing to challenge HHS’s actions on the COVID-19 vaccine recommendations, allowing the case to proceed to arguments). On August 19, independent expert groups, including the AAP, issued their own recommendations for COVID vaccines in infants and young children in contrast with CDC’s new recommendations.  On Aug 22, ACOG issued their own recommendations for pregnant patients.
June 9, 2025HHS Secretary Kennedy announces removal of all sitting members of ACIP.  
– In a post on X and a subsequent HHS press notice, Secretary Kennedy announces that all 17 sitting members of the CDC’s Advisory Committee on Immunization Practices (ACIP) are dismissed, to be replaced with new members selected by the Secretary. Kennedy says the move is “prioritizing the restoration of public trust above any specific pro- or anti-vaccine agenda.” The HHS Secretary does have the discretion to remove and nominate ACIP members, though no previous Secretary has dismissed all ACIP members at once. In a subsequent X post on June 11, Kennedy announces the nomination of eight new members to ACIP, several of whom have been critical of COVID-19 vaccines and have expressed concerns about harms caused by vaccinations more generally. In a later press release from September 15, HHS announces five more members to be appointed to ACIP, including several with a history of criticism of COVID-19 vaccine policies. 
June 17, 2025FDA announces National Priority Vouchers for expedited regulatory review of new drugs that support “U.S. national interest.
– FDA announces a Commissioner’s National Priority Voucher (CNPV) program, which can be “redeemed by drug developers to participate in a novel priority program” that shortens regulatory review time from 10-12 months to 1-2 months. FDA says it will determine the availability of vouchers for companies that are aligned with the “national health priorities” of: addressing a health crisis in the U.S.; delivering more innovative cures for the American people; addressing unmet public health needs; and, increasing domestic drug manufacturing as a national security issue. On October 16, FDA announced the first nine CNPV recipients, and on November 6, announced six more recipients.  The impact of this new priority voucher program on speeding drug approvals and onshoring drug manufacturing capacity is as yet unclear. In addition, there are several other existing priority review processes at FDA so adding another could strain FDA staff capacity at the same time there has been significant reductions in FDA’s staff and budget.  These strains have already slowed FDA review times in general.
June 18, 2025FDA approves lenacapavir – a new HIV prevention drug.
– FDA approves Gilead Sciences’ lenacapavir, a new injectable PrEP drug that has been shown to be highly effective at preventing HIV infection, and which requires just one dose every 6 months, making it the first ever twice-a-year drug option for HIV prevention. In September, CDC issued clinical guidance for use of injectable lenacapavir as PrEP, though that guidance did not include reference to transgender people, a group intentionally included in the clinical trials and at increased risk of HIV. FDA’s approval also precipitated a review by the World Health Organization (WHO) and on October 6, WHO pre-qualified lenacapavir for prevention of HIV. WHO pre-qualification can speed regulatory approval for the drug in many low- and middle-income countries with a high burden of HIV/AIDS and can also allow for global health mechanisms like the Global Fund to Fight AIDS, Tuberculosis and Malaria to procure the drug.
June 25-26, 2025The newly reconstituted ACIP makes recommendations and policy changes related to RSV and influenza vaccines, and designates new workgroups on hepatitis B, MMRV, and the childhood immunization schedule.
– ACIP votes to recommend respiratory syncytial virus (RSV) injections for babies and RSV vaccine for people 50 and older, and a ban on the use of thimerosal in multi-dose influenza vaccine vials. ACIP also agrees to stand up three new workgroups that will review the U.S. childhood vaccination schedule, hepatitis B guidance, and combination MMRV vaccine.  Subsequently, on July 3, CDC issued new RSV guidance that mirrored ACIP recommendations. On July 23, Secretary Kennedy enacted ACIP’s recommendation on thimerosal, rescinding federal recommendations for any influenza vaccines containing thimerosal (a change that only affects a very small percentage of the overall influenza vaccine market that is comprised of multidose vials).
July 1, 2025HHS alters program requirements and withholds funding from sex education and teen pregnancy prevention programs.
– HHS notifies all Teen Pregnancy Prevention (TPP) program grantees and Personal Responsibility Education Program (PREP) grantees in 46 states and territories that their material must align with President Trump’s executive orders, including those that ban the promotion of gender inclusivity, risk losing federal funding. TPP is a national grant program that funds grantees to replicate, develop, test, and evaluate evidence-based approaches to prevent teen pregnancy, while PREP awards grants to state agencies to use evidence-based models in educating adolescents on both abstinence and contraception. In August, the Trump administration cancelled a $12.3 million PREP grant to California after state officials refused to revise curricula in compliance with the EOs. In September 2025, 16 states and D.C. sued HHS alleging that the new PREP grant conditions are unlawful, unconstitutional, and harmful to gender diverse youth. Similarly, a federal judge blocked the HHS policy changes for TPP in October 2025.
July 2, 2025CDC deactivates its emergency response for H5N1 influenza (bird flu) and limits tracking and reporting of data on bird flu infections in humans and animals.
– CDC ends its emergency response for H5N1 bird flu in the U.S., which had been active since April 4, 2024. CDC reports the change is due to a decline in animal infections and no reports of human cases since February 2025. CDC also says data on the number of people tested for H5N1 will be reported only monthly, and no further data on infection rates in animals will be reported on the CDC website. Even so, reporting from states showed the number of H5N1 cases in birds, which had declined over the summer, began to increase again in fall 2025. However, much of the federal research and response efforts for H5N1 have been closed down or significantly limited following funding and staff cuts and a prolonged government shutdown. The limited federal tracking and reporting of H5N1 infections can slow identification of outbreaks and potentially slow response times.
July 9, 2025HHS Secretary Kennedy cancels a scheduled meeting of the U.S. Preventive Services Task Force (USPSTF).
– Secretary Kennedy cancels a meeting of the USPSTF several days before it was scheduled to take place, with no reason given and no re-scheduled meeting date provided. Typically, the task force meets three times a year, though no meeting has yet occurred under Secretary Kennedy. USPSTF is responsible for reviewing and recommending preventive health services. USPSTF recommendations have implications for what services insurers must cover with no cost-sharing, under the Affordable Care Act (ACA). Such services can include screening tests, behavioral counseling, and medications that can prevent diseases and illness (other than vaccines, which are tied to ACIP recommendations). However, along with other parts of the ACA, USPSTF has faced court challenges. On June 27 (prior to Kennedy’s cancelation of the meeting), while the Supreme Court ruled the ACA requirement that insurers cover USPSTF-recommended services is indeed constitutional, it also found that the HHS Secretary has the power to add and remove USPSTF members at will, which underscores the possibility that Secretary Kennedy may choose to dismiss some or all of the existing USPSTF members and appoint new members (as Kennedy has done with ACIP), or simply not name any new members, and has the power to choose not to adopt USPSTF recommendations. In light of Kennedy’s cancellation and the Supreme Court ruling, 104 public health focused organizations called on Congress to “protect the integrity of the USPSTF” through legislative action. The subsequent USPSTF meeting was scheduled to occur in November but that was also canceled, with HHS citing the government shutdown as the reason. Meetings in March 2026 and July 2026 were also canceled.
July 31, 2025FDA announces new safety label requirement for opioid pain medications.
– The FDA says will require safety labels on opioid medications so that users can better understand that risks of long-term opioid use. The updated labels should include a summary on the risk of addiction, misuse, and overdose, treatment guidance and the risk of higher doses, how to safely discontinue opioid use, drug interactions, digestive complications, and overdose reversal medications. Drug companies received notification letters and have 30 days to submit updated labels for review.
July 31, 2025HHS Secretary Kennedy swears in Susan Monarez as CDC Director.
– In a statement welcoming the newly Senate-confirmed CDC Director, Secretary Kennedy says Monarez has “unimpeachable scientific credentials” and he has “full confidence in her ability to restore the CDC’s role as the most trusted authority in public health.” However, 28 days later (on August 27) the White House removed Monarez from her position at CDC. According to Kennedy, she was removed because he lost trust in her ability to serve as CDC Director and to implement the policies of the Trump Administration. According to Monarez, she was removed because she would not provide “blanket approval” for vaccine policy changes in advance and would not fire, as requested by Kennedy, CDC employees without cause. On August 28, Secretary Kennedy announced in a letter to CDC staff that Deputy Health and Human Services Secretary Jim O’Neill would serve as acting CDC Director.
August 1, 2025Newly announced CDC policy prevents outside professional medical and public health organizations from participating in working group meetings of ACIP.
– Officials at HHS notify professional medical organizations such as the American Academy of Pediatrics (AAP), the American Medical Association (AMA), the American College of Obstetricians and Gynecologists (ACOG), and others that they will be excluded from joining ACIP working group discussions going forward. Professional groups representing medical doctors and other stakeholders in vaccine policies have long participated as non-voting members, including in ACIP working groups. Working groups are typically responsible for helping review available data about topics prior to ACIP meetings, and helping develop recommendation language for ACIP to vote on, as well as other activities in support of ACIP. While the outside groups can be present and can participate in full ACIP meetings, the new policy removes them from providing any input through working groups.
August 5, 2025HHS announces a “coordinated wind down” of $500 million in federal funding for mRNA vaccine research
– HHS announces that it will cancel and begin to wind down mRNA vaccine development activities funded through the Biomedical Advanced Research and Development Authority (BARDA). In total, HHS reports it is canceling 22 projects worth nearly $500 million because “these vaccines fail to protect effectively against upper respiratory infections like COVID and flu…Going forward, BARDA will focus on platforms with stronger safety records and transparent clinical and manufacturing data practices.”  mRNA COVID-19 vaccines are effective in preventing severe illness and death from the disease, and mRNA vaccine technology has potential applications for other infectious diseases, as well as chronic diseases like cancer. The cancellation removes the bulk of U.S. federal funding for mRNA research, leaving questions about future progress by the U.S. in this area of vaccine technology.
August 15, 2025HHS reinstates the defunct Task Force on Safer Childhood Vaccines.
– The original Task Force on Safer Childhood Vaccines, a federal panel created by Congress in 1986 “to improve the safety, quality, and oversight of vaccines” was disbanded in 1998, but HHS announces that the group will be re-instated at NIH with participation from officials at FDA, CDC, and other government agencies. The goal of the reconstituted Task Force will be “the development, promotion, and refinement of childhood vaccines that result in fewer and less serious adverse reactions than those vaccines currently on the market, and improvements in vaccine development, production, distribution, and adverse reaction reporting” to help increase federal oversight and investigation of vaccine injuries.  The Task Force will come together to develop recommendations to be submitted to Congress within two years, with updates every two years after. Reinstatement of this panel has been a goal of anti-vaccine advocates for years, including the Children’s Health Defense, the anti-vaccine organization Secretary Kennedy founded, which supported a lawsuit earlier in 2025 against Kennedy that sought to require him to reconvene the Task Force.
August 27, 2025FDA approves COVID-19 vaccines for 2025-2026, while limiting scope of approval to certain ages and risk profiles.
– FDA approves updated COVID-19 vaccines for 2025-2026, but also limited the approval to persons 65 and older and those between 18 and 64 with a health condition that puts them at higher risk for severe disease. Previously, the FDA had approved the use of vaccines for all ages (over 6 months) regardless of risk profile.
September 9, 2025MAHA Commission releases strategy to address childhood chronic disease.
– A new MAHA Commission strategy document outlines actions the federal government is taking or plans to take to address childhood chronic disease in the U.S. These include “more than 120 initiatives” that together represent “the most ambitious national effort ever to confront childhood chronic disease,” and which outline a “blueprint for the entire government” to address chronic disease. Elements of the strategy include: changing federal science and research priorities, reforming dietary guidelines, changing nutrition and food regulations through reducing additives and ultra-processed foods, and improving effort to raise public awareness about chronic disease. The strategy highlights the risks of vaccine injuries, fluoride in drinking water, among many other areas.
September 18, 2025Secretary Kennedy renews the declaration of the national opioid crisis as a public health emergency.
– In a declaration on an HHS website, Secretary Kennedy renews the declaration of the opioid crisis as a national public health emergency (PHE).  The opioid crisis was initially declared a public health emergency in 2017; renewal is required every 90 days to continue the PHE.
September 19, 2025Secretary Kennedy announces that the FDA will launch a new review of mifepristone.
– Secretary Kennedy announced that the FDA will undergo a review of the current Risk Evaluation and Mitigation Strategy (REMS) for mifepristone, due to new evidence including an April 2025 report from the Ethics and Public Policy Center (EPPC) which claims that mifepristone has a higher rate of adverse events than previously reported. This report has drawn criticism due to methodological flaws and lack of transparency regarding its data sources.
September 19, 2025ACIP makes several new recommendations related to MMRV and COVID-19 vaccines
– In its September 18-19 meeting, ACIP members vote on several new recommendations including to no longer recommend the combination MMRV (measles, mumps, rubella, and varicella) vaccine for children under the age of 4 and instead to recommend that children in this age group receive measles, mumps, and rubella (MMR) vaccine separately from the varicella vaccine (V). In addition, ACIP members vote to change what had been a universal COVID-19 vaccine recommendation (except for HHS’ recent change for healthy children and pregnant women) to “shared clinical decision-making”, including for those 65 and older, along with a recommendation for new language on risk-benefit for COVID-19 vaccinations. ACIP’s recommendations were adopted by CDC on October 6. While the separate MMR+V vaccines had been recommended as preferred by the CDC for many years, the combination MMRV provided an option for parents to reduce the number of injections their children receive. Now, insurers will no longer be required to cover this vaccine at no-cost. The new COVID-19 vaccine recommendations mean people of all age groups are now recommended to have an interaction with a health care provider (which could include a doctor, nurse, or pharmacist) to determine whether getting a COVID-19 vaccination is recommended for them. If that determination is made, insurers must cover the vaccine at no-cost, although it is possible that some consumers may face challenges in accessing providers in the first place or demonstrating that they have consulted with a medical provider seeking vaccination in some cases.    
September 22, 2025President Trump and Secretary Kennedy announce new actions to address autism spectrum disorder in the U.S.
– In a press conference and via an HHS press statement and Fact Sheet, President Trump and HHS Secretary announce several actions to address the issue of autism spectrum disorder (ASD) in the U.S. This includes FDA authorization for leucovorin, a treatment option for some children with autism, a regulatory change that will allow state Medicaid programs to newly cover leucovorin for the indication of ASD. President Trump and Secretary Kennedy also highlight what they say are risks of acetaminophen use during pregnancy and association with autism. The press release notes “HHS wants to encourage clinicians to exercise their best judgment in use of acetaminophen for fevers and pain in pregnancy by prescribing the lowest effective dose for the shortest duration when treatment is required.”  In his remarks, President Trump also implicated childhood vaccines as a potential risk factor for autism, though no new evidence was presented and that link has already been repeatedly and conclusively ruled out. In a subsequent press statement on September 22, HHS announced FDA was initiating a labeling change for leucovorin, and a safety label change for acetaminophen to include information about the “potential risks of acetaminophen so patients can make a more informed decision.” Public health groups and experts criticized the conclusions linking acetaminophen use in pregnancy and autism, and expressed doubts about leucovorin as a treatment for autism. President Trump’s remarks also precipitated a lawsuit filed on October 28 in Texas against the maker of Tylenol.
September 30, 2025FDA approves a new generic mifepristone product.
– The FDA approved Evita’s Solutions application for a generic version of mifepristone.   The approval included a reminder that the generic mifepristone is subject to the same  Risk Evaluation and Mitigation Strategy (REMS) as the brand-name.
September 30, 2025HHS awards $60 million in grants to support prevention of falls and related programs for older adults and those with disabilities.
– Secretary Kennedy announced 59 new grants totaling $60 million is being awarded to states, territories, tribes, and local organizations supporting older adults and Americans with disabilities, including programs for “preventing falls among seniors, managing chronic conditions…and funding dementia-capable programs.”
October 10, 2025Trump Administration fires thousands of HHS employees, including hundreds at CDC, during federal government shutdown.
– In the midst of a government shutdown and an ongoing federal funding impasse in Congress, the White House Office of Personnel and Management says over 4,000 federal workers are to be fired. At HHS, over a thousand workers are notified that they have lost their jobs, with most of those losses concentrated at CDC. Some of those job losses were reversed over the next few days, with HHS officials stating some notices were sent in error. Even so, as of October 14 it is estimated that about 600 CDC employees remain fired, including staff in areas such as injury prevention, health statistics, and Congressional relations. There is a question about whether such firings during a government shutdown are legal, and groups representing federal workers have filed lawsuits to halt these mass layoffs.
October 31, 2025FDA announces new restrictions on ingestible fluoride products for children.
– FDA announces new enforcement actions “to restrict the sale of unapproved ingestible fluoride products for children” and sends letters to health care professionals warning about the risks associated with these products. The actions come after FDA conducted a review and published a scientific evaluation of these products. In the announcement. FDA says it will be developing a “fluoride research agenda” and “the first national oral health strategy” for the U.S. in partnership with NIH and other HHS agencies.
November 10, 2025FDA announces a warning label change on hormone replacement therapy (HRT) products for addressing symptoms of menopause.
– In a press release, a fact sheet, and a live press event, FDA leaders announce that they will initiate the removal of broad “black box” warnings from HRT products for menopause. The FDA also announces approvals for two new drugs for menopausal symptoms. According to the FDA, women have been “under-utilizing approved therapies” since the “black box” warnings about risks associated with the drugs were placed on these products over 20 years ago. Labels will be rewritten with guidance saying that there are long-term health benefits if HRT is begun within 10 years of the onset of menopause.
November 19, 2025CDC changes language on its website to say a link between vaccines and autism cannot be ruled out.
– A CDC website providing information to the public on Autism and Vaccines, is changed to include language saying “studies have not ruled out the possibility that infant vaccines cause autism.” The new site also discusses the “state of the evidence” on common childhood vaccines and supposed links to autism. The new language is a reversal from previous CDC statements saying “vaccines do not cause autism,” and contradicts the long established scientific consensus that there is no link between vaccines and autism. The new CDC webpage language has been criticized by professional medical organizations such as the American Medical Association and the American Academy of Pediatrics, as well as autism organizations such as Autism Speaks and the Autism Science Foundation.
November 21, 2025CDC staff ordered to end all monkey research programs, potentially affecting development of prevention tools for HIV and other infectious diseases.
– According to reports, CDC staff are ordered to halt its monkey research program by the end of 2025. This program has helped develop HIV prevention tools such as pre-exposure prophylaxis (PrEP) and microbicides, as well supported prevention research for other infectious diseases.
November 28, 2025Internal FDA communication proposes stricter federal requirements for testing and approving vaccines.
– According to reports, the head of FDA’s Center for Biologics Evaluation and Research (CBER), which is responsible for regulating vaccines, issues an email to staff proposing new, stricter federal requirements for vaccine testing, evidence, and approval. The email states that in the future FDA will “demand pre-market randomized trials assessing clinical endpoints for most new products” and that FDA “will not be granting marketing authorization to vaccines in pregnant women” without this kind of evidence. Newly developed pneumonia, influenza, and COVID-19 vaccines are specifically mentioned as vaccines that would be subject to these new requirements. The rationale given for this policy change is a new analysis of vaccine safety data indicating “COVID-19 vaccines have killed American children,” though no evidence to support that statement is provided in the email.
December 5, 2025ACIP votes to end recommendation that all newborns receive hepatitis B vaccine dose at birth
On the second day of the Advisory Committee on Immunization Practices’ (ACIP) December 4-5 meeting, members vote to end a long-standing recommendation that all newborns in the U.S. receive a dose of hepatitis B vaccine. The committee now recommends parents of infants born to mothers who test negative for hepatitis B consult with their provider to help decide if and when their child should receive the first hepatitis B dose. ACIP continues to recommend that infants born to mothers who test positive for hepatitis B, or whose hepatitis B test status is unknown, receive the first hepatitis B vaccine dose at birth. A recommendation from ACIP becomes part of the official CDC immunization schedule once it is adopted by the CDC director.
December 30, 2025HHS ends certain requirements for state reporting of immunization data to the Centers for Medicare and Medicaid Services (CMS).
December 30 letter from the Centers for Medicare and Medicaid Services (CMS) informs state health officials that starting in 2026, states will no longer be required to report several measures related to immunization status to CMS. Specifically, CMS removes the following from its “Child and Adult Core Sets”: “Childhood Immunization Status”, “Immunizations for Adolescents”, “Prenatal Immunization Status: Under Age 21”; and “Prenatal Immunization Status: Age 21 and Older.” In addition, in its letter CMS informs state health officials it will “explore options to facilitate the development of new vaccine measures that capture information about whether parents and families were informed about vaccine choices, vaccine safety and side effects, and alternative vaccine schedules” and “how religious exemptions for vaccinations can be accounted for.” Data reported by states and included in the Child and Adult Core Sets are used by Medicaid and CHIP to monitor access to and quality of health care for their beneficiaries, so an absence of this data could make monitoring immunization coverage in this population more challenging.
January 5, 2026HHS announces changes to the federal childhood vaccination schedule that reduce the number of routinely recommended vaccines
Health and Human Services (HHS) issues a memo implementing major changes to the government’s recommended vaccination schedule for children. Under the new guidelines, there are vaccines for 11 diseases recommended for all children, down from 17 diseases a year ago. In addition to COVID-19 (which HHS stopped recommending for all children back in October 2025), the new schedule no longer recommends routine vaccinations for five other diseases: rotavirus, COVID-19, influenza, hepatitis A, hepatitis B, and meningococcal. These vaccines have been moved from routine recommendation to “shared clinical decision making,” a process that is “individually based and informed by a decision process between the health care provider and the patient or parent/guardian.”  The HPV vaccine remains recommended for routine vaccinations, though under the new guidelines HHS reduces the number of recommended doses of HPV drops from two or three (depending on age of initial vaccination) to one. Coverage for all of these immunizations should remain the same through public and private insurance mechanisms. On March 16, 2026, a federal judge issued a ruling that stayed changes to the vaccine schedule from being implemented, as the government did not follow required procedures. On April 29, HHS appealed the judge’s stay and court review continues.
February 3, 2026BARDA opens solicitations for a $100 million prize program for development of novel antivirals targeting dengue, West Nile, and other viruses.
In a news release, HHS’ Biomedical Advanced Research and Development Authority (BARDA) announces it is opening solicitations for a share of a new $100 million SMART Antiviral prize intended to speed the development of “broad-spectrum, small-molecule antiviral therapies” targeting families of viruses that include dengue, Zika, West Nile, and Chikungunya. This first stage is designed to receive solicitations at the concept stage, with solicitations for further development stages anticipated in the future.
February 4, 2026Trump Administration instructs CDC to rescind $600 million in public health funds going to four Democratic-led states
According to reports, the Office of Management and Budget ordered CDC to cut $600 million in funding that had been earmarked for state and local public health programs in California, Colorado, Illinois, and Minnesota. Most of the funding cuts affect programs focused on HIV and STD prevention, are are to be terminated because they “do not reflect agency priorities” according to an HHS spokesperson. On February 11, affected states filed a lawsuit in federal court against these cuts, and on February 12 a federal judge issued a temporary restraining order blocking the cuts from taking effect.
February 10, 2026FDA refuses to review Moderna’s license application for its investigational mRNA-based influenza vaccine
Moderna announces it received a “Refusal to File” letter from FDA stating that the agency will not initiate a review of the company’s biological license application for its investigational mRNA-based seasonal influenza vaccine. According to FDA, the refusal is due to the company’s use of an inadequate comparison arm in its study. Moderna states the letter is “inconsistent with previous written communications” with FDA staff. On February 18, Moderna announced that FDA had reversed its decision, and will now review the application, following further discussions with the company.
February 18, 2026FDA to allow drug approvals with evidence from one clinical trial rather than two
In an opinion article published in the New England Journal of Medicine, FDA leaders announce a new FDA policy that will make the default requirement for FDA approvals to be results from one clinical trial instead of the prior requirement of two clinical trials.  The stated goal of the change is to accelerate the approval and availability of new medicines.
February 19, 2026CDC delays February ACIP meeting
HHS/CDC announces the ACIP meeting previously scheduled for February 25-27 will be postponed. The postponement occurs amid an ongoing federal lawsuit filed by the American Academy of Pediatrics (AAP) and other medical groups that argues the recent revisions made by HHS to the federal child immunization schedule were arbitrary and violated administrative procedures and seeks to have the ACIP panel appointed by HHS Secretary Kennedy removed and replaced and its decisions overturned. On February 26, CDC announced the ACIP meeting had been rescheduled for March 18-19. On March 16, 2025, the judge ruled that 13 of 15 ACIP member appointments did in fact violate administrative procedures and their appointments are stayed along with any ACIP votes since the appointments were made. As a result, the planned March 18-19 ACIP meeting has been canceled.
February 23, 2026FDA launches new framework for speeding development and approval of therapies for rare diseases
FDA announces draft guidance for drug developers that seek approval for targeted, individualized therapies. The new framework outlines new approaches to regulatory review and evidence requirements on the safety and efficacy for rare diseases, given that traditional randomized clinical trials may not be feasible for these conditions.
March 4, 2026HHS Postpones Third Straight Meeting of US Preventive Services Task Force (USPTF)
USPTF, which makes recommendations on preventive health care services, has not met since March of 2026. Five of the 16 USPTF members’ terms have ended as of January 1 and have not been replaced.  
April 10, 2026HHS Publishes Updated ACIP Charter
The Trump Administration published an updated version of the Advisory Committee on Immunization Practices (ACIP) charter. The revised charter features language that broadens the inclusion criteria for ACIP member expertise, including mentions of vaccine safety and recovery from serious vaccine injuries as areas of expertise that members can possess.  The charter language was updated yet again in May, with the newest version published on May 27, 2026. The newest version places oversight of ACIP more directly under the CDC director, includes language that emphasizes potential gaps or limitations in vaccine data, and does not commit to a set schedule of ACIP meetings annually (previously, the charter required three ACIP meetings a year).
April 22, 2026CDC Study on COVID-19 Vaccine Effectiveness Held Back From Publication
Reports find that Jay Bhattacharya, who is overseeing CDC operations while the Director position remains unfilled, held back publication of a CDC study on the effectiveness of the COVID-19 vaccine over the 2025-2026 winter season. The study was scheduled to be published in the CDC’s flagship MMWR publication on March 19, but Bhattacharya objected to the study’s design, although it is a very common design that has been used to study vaccine effectiveness in dozens of prior published studies. The study had found vaccination cut the likelihood of emergency visits due to Covid by 50 percent and of hospitalizations by 55 percent. Eventually, the study was published in a different journal in June 2026.
May 29, 2026 Executive Order On Childhood Vaccines Directs HHS to Review and Update U.S. Childhood Vaccine Schedule
The White House issues an executive order titled “Realigning United States Core Childhood Vaccine Recommendations with Best Practices from Peer, Developed Countries” that instructs federal agencies, including HHS, that the childhood vaccine schedule “should be aligned with scientific evidence and best practices from peer, developed countries while preserving access to vaccines currently available to Americans.” This follows an earlier memorandum from December 5, 2025 instructing HHS to align the childhood vaccine schedule with that of “peer, developed nations.”
June 18, 2026FDA Advisory Committee Unanimously Recommends Approval of mRNA Influenza Vaccine
The Food and Drug Administration’s (FDA’s) Vaccines and Related Biological Products Advisory Committee (VRBPAC) votes unanimously to recommend approval of Moderna’s mRNA vaccine candidate for older adults. In February of this year FDA had said it would not review Moderna’s application for this vaccine, but several weeks later reversed course and agreed to review after Moderna proposed a revised approach to regulatory review. The FDA reports it is likely to make its decision on this vaccine by August 5 this year.
June 30, 2026Secretary Kennedy Terminates COVID-19 Emergency Use Authorization Declarations for Drugs, Biological Products, and Medical Devices
HHS announces Secretary Kennedy has terminated COVID-19 Emergency Use Authorization (EUA) declarations for drugs and biological products and for medical devices after determining these authorizations are no longer needed. The declaration for drugs and biological products will terminate 12 months after the Secretary’s determination, while the declarations for medical devices will terminate 180 days after the Secretary’s determination. EUAs for COVID-19 vaccines had already been terminated.
August 10, 2026Executive Order on Vaccines Instructs HHS and States to Realign Childhood Vaccine Recommendations
The White House releases a new Executive Order (EO) titled “Delivering Gold Standard Childhood Vaccine Recommendations for Americans” that states U.S. childhood vaccine recommendations should be “aligned with scientific evidence and best practices from peer, developed countries,” and sets out three categories of recommended immunization (echoing the January 5 HHS memo described above that issued a new federal childhood vaccine schedule, which has been put on hold by a federal judge). The new EO also directs the HHS Secretary to offer some childhood vaccines such as measles, mumps, and rubella (MMR) as “single vaccines rather than combination products,” and to align vaccine recommendations with findings to be released by a federal panel known as the “HHS Task Force on Safer Childhood Vaccines.”
News Release

Analysis: At Least 37 States Have Medicaid State Directed Payments for Hospital Services That Could Be Reduced by the 2025 Reconciliation Law Limits

States with the Biggest Potential Reductions in Medicaid Payments to Hospitals Include California, Illinois, Kentucky, Texas, North Carolina, Louisiana, Arizona and Michigan

Published: Aug 14, 2026

An estimated $60 billion in federal Medicaid spending in 37 states (including the District of Columbia) would likely exceed new federal limits on state directed payments for hospital services once fully implemented, a new KFF analysis finds.

The 2025 reconciliation law made major changes to Medicaid eligibility and financing, including new limits on how much states can direct Medicaid managed-care organizations to pay for certain services, including hospital care.

The eight states with the biggest potential reductions in Medicaid payments to hospitals account for half of the total: California ($7.4 billion), Illinois ($4.0 billion), Kentucky ($3.9 billion), Texas ($3.5 billion), North Carolina ($3.4 billion), Louisiana ($3.3 billion), Arizona ($3.0 billion) and Michigan ($2.6 billion).

In the past, states were allowed to direct managed care plans to pay hospitals and other providers up to the average commercial rates for such services. Once implemented, the new law limits such payments in most states to Medicare payment rates, which typically are substantially lower than commercial rates. In the 10 states that have not expanded their Medicaid programs under the Affordable Care Act, payments are capped just above Medicare rates.

The Trump administration in June 2025 issued a proposed rule to implement the change but has not yet finalized those regulations. The analysis assesses the scope of federal funding for hospital services that could be affected once the new limits are fully in place, including insights into how the magnitude of the changes will vary by state.

The estimates do not project actual revenue losses for hospitals annually, which would be affected by other coverage changes, provider tax changes as well as state responses to the new limits.

States with state directed payments that exceed the new limit could take a range of actions in response, including increasing base payment rates for hospital services, though their ability to do so may be limited by other new restrictions on financing mechanisms, such as provider taxes. Hospitals’ ability to absorb reduced payment rates also varies and could pose particular challenges for hospitals with low operating margins, including many rural hospitals and hospitals with relatively large numbers of Medicaid patients.

At Least 37 States Have Medicaid State Directed Payments for Hospital Services That Could Be Reduced by the 2025 Reconciliation Law Limits

Published: Aug 14, 2026

The 2025 reconciliation law reduced federal Medicaid spending by an estimated $911 billion from 2025 through 2034, some of which stems from new restrictions on Medicaid state directed payments (SDPs) for hospital and other health care services. While states are generally prohibited from directing how managed care organizations (MCOs) pay for care, states can implement SDPs that require MCOs to increase rates or set minimum rates for specified Medicaid services. In authorizing SDPs and allowing states to require payments up to the rates paid by private insurers, the Centers for Medicare and Medicaid Services (CMS) aimed to help states improve access to care and provider participation. A 2024 rule on Medicaid managed care that codified rules for SDPs increased states’ use of SPDs and associated federal spending, spurring opponents to argue that private insurance rates were too high a threshold. Many states that contract with MCOs use SDPs to make uniform rate increases that function like supplemental payments in fee-for-service (FFS) Medicaid. This issue brief explores the state-level implications of forthcoming restrictions for SDPs, focusing on SDPs that pay for hospital services because KFF estimates that 84% of SDP spending is directed toward hospital services. Two companion issue briefs provide a summary of forthcoming changes and estimate current SDP spending before forthcoming restrictions take effect.

The analysis estimates the amount of current federal spending on SDPs for hospital services that exceeds the new limits established by the 2025 reconciliation law. In practice, the new limits will be gradually phased in over time for existing SDPs. In some cases, spending on SDPs could also be affected by new limits on provider taxes prior to the SDP limits taking effect, or the two changes will affect SDPs concurrently. The findings of this analysis demonstrate the potential amount of federal funding for hospital services that would be above the new limits (when fully implemented), providing a sense of the eventual magnitude of the changes and how they vary by state. The focus is federal funding because many states finance SDPs through either provider taxes or intergovernmental transfers (IGTs), making it difficult to determine the amount of net revenues health care providers receive. This analysis finds that:

  • At least 37 states have Medicaid state directed payments for hospital services that could be reduced by the 2025 reconciliation law limits based on their current payment policies (Figure 1).
  • An estimated $60 billion in current federal spending for hospital services through SDPs is above new limits and could be reduced when the new limits on SDPs are fully implemented.
  • More than half of the estimated potential reductions in federal SDP spending on hospital services above new limits comes from eight states (CA, IL, KY, TX, NC, LA, AZ and MI).
At Least 37 States Have Medicaid State Directed Payments for Hospital Services That Could Be Reduced by the 2025 Reconciliation Law Limits (Choropleth map)

Among SDPs which started on January 1, 2024 or later and were approved through May 12, 2026, KFF estimates that SDPs with payments for hospital services in 37 states are likely affected by the limits. Of those SDPs, KFF was able to estimate the amount of spending directed to hospitals that exceeded the new payment limits in 131 “preprints” filed by 35 states (see Methods for a description of KFF’s criteria for including preprints in the analysis). Preprints are application forms that document how states direct Medicaid managed care plans to pay providers using SDPs. Preprints are the only national source of data on SDPs but are limited because there are gaps in data provided by the preprints. For example, the preprints include states’ projected spending on SDPs but not actual spending, do not document how total spending is allocated across different services when a single SDP governs payments for multiple services, and omit details about the required payment rates for about half ($39.6 billion) of all hospital spending in this analysis. Such data gaps required KFF to impute missing data in several cases and rely on the best available sources of data in others, contributing to uncertainty in the estimates (see Methods). Although the estimated amounts of spending above new limits are uncertain, there are 37 states with SDPs that pay for hospital services using a rate that is based on average commercial rates. Those SDPs will likely no longer be permissible at current rates under the new law.

The 2025 reconciliation law established new payment limits for SDPs, capping them at or near Medicare rates instead of average commercial rates (ACR). The new limits are set in relation to a “benchmark,” which is a standardized rate that measures MCO rates relative to other payment rates such as Medicaid FFS, Medicare FFS, and average commercial (private) rates. Before the reconciliation law passed, CMS capped SDP payment limits at average commercial rates, which average about double what Medicare pays. (Prior federal rules specified average commercial rates were the limit for hospital services, nursing facility services and professional services at academic medical centers. CMS informally applied the same limit to other services.) Under the reconciliation law limits, SDP payment rates may not exceed 100% of the Medicare payment rate in states that have adopted the Affordable Care Act (ACA) Medicaid expansion (“expansion states”) and 110% of the Medicare payment rate for non-expansion states. In June 2025, CMS released a proposed rule that would implement the new changes.

To estimate the share of hospital spending above new limits, KFF started with estimated SDP spending for hospital services from its prior analysis, which also captured states’ estimated base payment rates for hospital services (e.g., without the SDP) and the final payment rates after accounting for SDPs. As noted in the prior brief, many SDPs indicate the type of benchmark used (e.g., average commercial rates or Medicare rates) but do not provide the payment level (e.g., 100% or 80% of average commercial rates). For hospital services with SDPs benchmarked to commercial rates, KFF estimated the Medicare-equivalent rates using RAND’s state-level inpatient and outpatient ratios of commercial to Medicare rates. KFF compared the base and final payment rates to the Medicare-based limits to estimate the amount of SDP spending that would fall above the new Medicare-related limits when the law is fully implemented (see Methods). Making assumptions about missing payment rate information and about conversions to Medicare rates contributes to the uncertainty of KFF estimates.

New limits on SDPs are likely to decrease Medicaid payments for hospital services in at least 37 states (Figure 1). There are 37 states with SDPs that direct payments for hospital services, all of which have at least one SDP with established payment rates for hospital services estimated to exceed the new limits established by the 2025 reconciliation law. Additional states could be affected by the new limits if there are SDP preprints that CMS has not yet approved or published, and all states are limited in their ability to create new SDPs. Some states may not know whether they will be able to implement planned SDPs. For instance, Colorado submitted an SDP proposal to CMS on June 27, 2025 that would pay hospitals using average commercial rates. The proposal notes that the program could represent an additional $378 million in reimbursements to Colorado hospitals. However, as of July 20, 2026, CMS had not published the preprint on its approved list (although it was posted as of August 11, 2026).

An estimated $60 billion in current federal spending for hospitals through SDPs could be reduced once the new limits take full effect (Figure 2). This represents 64% of federal spending on SDPs and 77% of federal spending on SDPs for hospital services. The $60 billion is an estimate of the amount by which federal payments would currently be above the new limits if those limits were in effect today. It does not represent the amount by which federal payments would be reduced in any given year, since these limits will be phased in over time starting in January 2028 and will fully take effect at different times in different states.

An estimated  billion in current federal spending for hospitals could be reduced when new limits take full effect (Stacked Bars)

The $60 billion in federal SDP spending above new limits does not represent annual estimates of hospitals’ Medicaid revenue losses. Although the new limits on SDPs have major implications for hospital finances, spending above the new limits is not equivalent to the yearly change in revenues hospitals might expect. Actual revenue losses for hospitals could be higher or lower because of interaction with other policy changes and state and hospital behavioral responses:

  • Additional Medicaid policy changes. The 2025 reconciliation law is estimated to reduce federal Medicaid spending by $911 billion, with several policies expected to reduce hospital revenues. For example, changes to provider taxes could affect how states finance the state share of Medicaid. In a proposed rule on the provider tax changes, CMS reports that the changes to SDPs in total (which include providers other than hospitals) are estimated to reduce federal Medicaid spending by $510 billion from 2026-2034, but that $155 billion of those reductions are also part of the reduced spending stemming from changes to provider tax rules. Beyond provider tax changes, hospital revenues will be affected by new work requirements and other provisions that could result in fewer patients being covered by Medicaid, and more people being uninsured.
  • State Medicaid dollars above new limits. New SDP spending limits may also reduce state spending, but this analysis only includes the federal share. The state share is excluded because states fund some or all the state share for SDPs with provider taxes or intergovernmental transfers from entities such as public hospitals. In such cases, it is unclear how much the state share represents new revenues to hospitals in aggregate.
  • Possible offsets from states. States might offset some of the reductions in SDP revenues by increasing base payment rates for hospital services, although their ability to do so may be limited given new restrictions on financing mechanisms like provider taxes.

More than half of the estimated potential reductions in federal SDP spending on hospital services comes from eight states (Figure 3). California ($7.4 billion), Illinois ($4.0 billion), Kentucky ($3.9 billion), Texas ($3.5 billion), North Carolina ($3.4 billion), Louisiana ($3.3 billion), Arizona ($3.0 billion), and Michigan ($2.6 billion) have the largest estimated amounts of federal SDP spending for hospital services above new limits. Although the analysis focused on federal spending, if total spending were instead used, the same eight states would still account for more than half of spending above the new limits. Rhode Island, Delaware, and New Hampshire have the smallest estimated amounts of federal SDP spending for hospital services above new limits (accounting for a combined total of $0.4 billion in federal spending).

More than half of the estimated potential reductions in SDP spending on hospital services comes from eight states (Pie Chart)

The dollar amount of SDP spending above new limits may not indicate which states could have the biggest proportional effects when the law is fully implemented. For instance, although California has the largest estimated amount of hospital SDP spending above new limits, it also had the highest Medicaid spending in 2024. It is possible that other states’ spending over the new limits may account for a larger share of those states’ Medicaid spending. Data for Medicaid hospital spending by state in 2025 and 2026 are not yet available, making it difficult to look at SDP spending as a share of total Medicaid spending across states.

Across states, there is variation in the share of SDP spending that is estimated to be above new limits (Figure 4). Estimated spending above new limits as a share of all hospital SDP spending range from 9% in New Hampshire to 100% in two states (Louisiana and DC). In KFF’s analysis of SDP spending for hospital services above new limits, in 27 states at least 70% of SDP spending for hospital services is above the new limits.

KFF includes Minnesota and Missouri in the 37 states that are likely affected because they both have SDPs that pay for hospital services using a benchmark linked to average commercial rates. However, the preprints for those SDPs did not meet KFF’s inclusion criteria for this analysis because data were insufficient to estimate the amount of spending at risk under the new limits. As a result, Minnesota and Missouri are excluded from the analyses of the amount of SDP spending at risk under the new limits (see Methods).

A key factor in determining how much of the SDP spending exceeds the new payment limits is the level of base payment rates. States with lower base rates may be spending more through SDPs to bring total payment rates up to 100% or 110% of Medicare rates, and therefore, more of the SDP will fall below the new limits established by the 2025 reconciliation law. Conversely, in states where the vast majority of estimated SDP spending exceeds the new limits, base payments are estimated to be at or near the reconciliation law limits.

Hospitals will likely vary in how they are impacted by lower SDP spending, and it is unknown how the new limits will affect access to care among Medicaid enrollees. The effects for specific hospitals will depend on how much they are currently receiving in SDPs, how much their revenues decline as the new limits take effect, the interaction with changes to provider taxes, and how dependent they are on SDP revenues. Effects will vary across states but also within states because states may direct SDPs to a subset of hospitals, or sometimes a single hospital, and among eligible hospitals, SDPs vary with Medicaid patient volume. Hospitals’ ability to absorb reduced payment rates also varies. For hospitals with relatively high operating margins (such as for-profit hospitals and those serving relatively large shares of commercial patients), changes to SDP revenues might be more easily absorbed. On the other hand, hospitals with relatively low operating margins (like rural hospitals and those serving relatively large shares of Medicaid patients) may adapt in ways that affect Medicaid enrollees’ access to care, such as by cutting service lines or closing.

Across states, there is variation in the share of SDP spending that is estimated to be above new limits (Bullet Bars)

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

Patrick Drake, an independent consultant, contributed to the analysis of SDP data.

KFF appreciates the contributions of external reviewers who provided comments on earlier versions of this analysis.

Methods

Data source: This analysis uses data available from the list of approved state directed payment preprints published by the Centers for Medicare and Medicaid Services (CMS) as of May 12, 2026. The approved state directed payment (SDP) preprints are PDF versions of forms that are completed by states and approved by CMS. States are required to seek approval using such a preprint for any SDP that requires managed care organizations (MCOs) to pay for services at any rate other than fee-for-service (FFS) Medicare or Medicaid rates. The approved preprints are often posted online 6–12 months after their start date, although some approved preprints are posted online much later.

KFF developed a Python script to download the available PDFs, extract relevant data from them, and standardize certain fields. Each preprint was turned into one row in a spreadsheet. Data from tables within the preprint were extracted and converted into separate tables in KFF’s data file with each row in the preprint table converted into a row in the spreadsheet table.

SDP preprint inclusion criteria: KFF included all SDPs in the analysis with a rating period start date of January 1, 2024, onward for the 50 states and Washington DC (hereafter referred to as a state). Puerto Rico was the only territory that had published SDPs, which were excluded. In each case, KFF only kept the most recent preprint for any given SDP. For example, if an SDP had an initial approval in 2024 and then renewals in 2025 and 2026, KFF would only include the 2026 renewal in the final dataset. Out of the 304 preprints included in this analysis, 23 (totaling $8.6 billion in federal spending) ended in calendar year 2024.

A small number of SDP preprints were excluded due to file formatting or data validity issues. Specifically:

  • Data from five preprints were encoded differently, so the data could not be programmatically extracted into the dataset and were therefore excluded from the analysis (two from New Hampshire, one from Ohio, and two from Florida, totaling $89 million in federal spending for one year).
  • Data from preprints that had obvious data quality issues were excluded from this sample. For instance, two were from Illinois (which projected total annual spending of more than $100 billion) while one from Minnesota did not report spending data in the preprint.

KFF also reviewed all preprints with end dates prior to July 1, 2025, and excluded preprints for the following reasons.

  • The preprint was likely funded from COVID-19 relief dollars (including the increased federal funding for home care from the American Rescue Plan Act) and so unlikely to still be in place.
  • The preprint was likely combined into a different preprint when renewed or was otherwise renamed when renewed.
  • The preprint ended in 2024, and online research suggests that the payment was discontinued.

For purposes of identifying which states are likely affected by new limits, KFF manually reviewed SDPs in Minnesota and Missouri, which were the only two states with at least one preprint directed to hospital services but which did not meet the inclusion criteria. Upon review, KFF determined that preprints for hospital services in these states would also likely be affected.

See Methods Table 1 for a list of the inclusion criteria, the counts of preprints after each criterion was applied, and the federal spending for preprints that were retained at each stage.

Calculating total spending on SDPs: This analysis used the states’ projected total, federal, and state spending from the preprint. Most preprints are for a one-year period, but some are for longer or shorter periods. In such cases, KFF adjusted the data to be a one-year equivalent. When preprints were for periods shorter than 12 months, dollars were scaled up (e.g., if the preprint was for 6 months, the spending was multiplied by two) and for preprints that were for periods longer than 12 months, spending was scaled down (e.g., retaining two-thirds of spending if the preprint extended for 18 months).

KFF also manually reviewed the federal spending numbers because some states reported them as percentages of total spending and others reported them as dollar amounts. Manual review ensured the Python script had adequately handled the different reporting structures.

Calculating SDP spending by service type: For preprints that made payments for multiple service types (which accounted for $32.4 billion in federal spending), spending was apportioned across service types.

  • For SDPs directed to hospital and non-hospital services, 90% of spending was allocated to hospital services.
  • For SDPs directed to both inpatient and outpatient hospital services, 68% of hospital spending was allocated to inpatient services and 32% was allocated to outpatient services. Distinguishing between the two is important because states sometimes use different benchmark rates for each.

Apportioning spending across service types is difficult, and KFF used a variety of sources to develop the most realistic assumptions feasible. KFF analyzed data on Medicaid spending, including CMS-64 spending by service type, data on Medicaid spending by service type from the National Health Expenditures, the Congressional Budget Office Medicaid baseline, and existing studies on hospital payment policies such as those from the Medicaid and CHIP Payment and Access Commission (MACPAC). All of those data points suggest that the vast majority of SDP spending pays for hospital services, and $53.1 billion out of the $60.5 billion in federal spending from preprints directed to a single provider type went to hospital services. KFF also strove to use an assumption that resulted in estimates of hospital SDP spending that are similar to what could be expected on the basis of other data and research as described above.

When identifying the service types in the preprints, the Python script attempted to align service types between preprint Table 2 (which specifies payment rates for sets of providers) and preprint Question 20 (a checklist of services included in the SDP). In many cases, this alignment involved some uncertainty, requiring manual review and classification of service types.

Identifying benchmarks for MCO payments: The most common type of SDPs requires MCOs to make payments that are on top of the regular base payment rate (as opposed to limiting or replacing the negotiated rate). In such cases, payments are measured using a “benchmark” or standardized rate to compare the MCO rates to other payment rates, such as those of Medicaid FFS, Medicare FFS, or the average among commercial payers (“average commercial rates”). KFF used the Python script to identify the applicable benchmark type from the preprint but also manually reviewed the data since states sometimes used inconsistent terminology to report the same benchmarks.

Identifying payment levels: To identify how current payment rates align with the new limits on SDPs in the reconciliation law, KFF first needed to identify payment levels in the preprints. The level is specified as a percentage of the benchmark (e.g., 90% of average commercial rates or 140% of Medicare rates). Both types of payments were pulled from Table 2 when available. Payment rates for inpatient and outpatient hospital services were tracked separately with each row in Table 2 when applicable.

Hospital analysis: The methods above were used in a previous KFF analysis to estimate current SDP spending before new limits take effect. Additional methods below were incorporated into this analysis.

Hospital analysis inclusion criteria: For the analysis of how SDP spending levels align with new limits on SDPs in the 2025 reconciliation law, KFF further limited the analysis to:

  • SDPs with inpatient or outpatient hospital services as a service type in Question 20,
  • Those required to report a benchmark, and
  • Those benchmarked to Medicare or average commercial rates.

Of the 131 preprints included in the hospital spending analysis (accounting for $78.0 billion in federal spending on hospital services), 35 did not include payment levels in Table 2 (accounting for $39.6 billion in federal spending on hospital services). Payment rates were missing for the relevant preprints because states left Table 2 incomplete and instead noted that rates were reported in attached addendums, which CMS generally does not make publicly available (some rate description addendums were at the end of the preprint, but they were not included in this analysis because they were not in a machine-readable format). KFF submitted a Freedom of Information Act request to access the addendum data on August 25, 2025, but, as of July 21, 2026, had not received the addendums or any information about whether the addendums would be available or the timing of their availability.

Comparing payment levels to new limits in the 2025 reconciliation law. In cases where rates were benchmarked to commercial rates, KFF first converted the rates to a Medicare-equivalent rate using state inpatient and outpatient commercial-to-Medicare price ratios from the 2024 RAND Price Transparency Study. The RAND price ratios are approximations, and actual commercial-to-Medicare price ratios may be higher or lower than what was used in the KFF analysis. For instance, RAND price ratios were derived from claims data from 2020–2022, and so may have changed between then and the sample period. RAND price ratios were also based on a sample of claims and are higher than some from other estimates at a national level, but have been used by other researchers to analyze state directed payments.

For SDP preprints that were missing the payment level, KFF estimated the payment rates for hospital services using the payment levels in other preprints. KFF first created national and state-specific (when possible) median payment rates for the following measures:

  • Inpatient rates among SDP preprints that are benchmarked to average commercial rates and Medicare rates, and
  • Outpatient rates among SDP preprints that are benchmarked to average commercial rates and Medicare rates

Where feasible, the analysis used the applicable state-specific rate (eight states—Georgia, Kentucky, Louisiana, New Mexico, Nevada, New York, Pennsylvania, and Washington). In other cases, the analysis used the applicable national rate (six states—Arizona, California, Hawaii, Illinois, Texas, and Wisconsin). Additionally, for North Carolina, KFF used the state-specific rate for outpatient services and the national rate for inpatient services. KFF’s imputed benchmark rates were more conservative than a RAND analysis of SDPs, in which all missing rates benchmarked to commercial rates are assumed to be 100% of average commercial rates.  For the remaining states, KFF had complete payment rate information from the preprints.

Estimating spending on hospital services above new limits: When the total payment rate (accounting for base payments and the SDP) was below the new limit (100% in expansion states or 110% in non-expansion states; expansion status was pulled from KFF’s Status of State Medicaid Expansion Decision tracker), the SDP was assumed to already be under the new limit and so would not need to be reduced. This was the case for 27 preprints, representing $2.2 billion in federal hospital spending. All other SDPs were assumed to be affected. When the base rate was above the new limit, 100% of the SDP was estimated to be above the new limit (this was the case in 50 SDPs, accounting for $15.0 billion in federal hospital spending).

For SDPs where the base rate was below the new limit, but the total rate of the SDP was above the new limit (a little less than half of preprints in the sample), KFF estimated the amount of federal spending above new limits as detailed below and in Formula 1.

  1. The calculation was done separately for each provider row in Table 2, using the federal spending apportioned to each service line (as described above in “Calculating SDP spending by service type”) to calculate the estimated spending above new limits.
  2. KFF estimated the difference between the total rate and the maximum rate allowed under the 2025 reconciliation law (both measured relative to Medicare payment rates, as described above), which represents the “portion of increase from the SDP above limit.”
  3. KFF also estimated the difference between the total rate and the base rate, which represents the “increase from SDP.”
  4. Those two rates were used to estimate the percentage of the SDP spending that would be above new limits.
  5. That share was multiplied by the “apportioned federal spending” for the specific service line (i.e., the amount of SDP spending calculated by service type) to estimate the amount of SDP spending above new limits.
  6.  The total rate comes from the “Total Payment Level” column of Table 2 (converted into a Medicare-equivalent rate when benchmarked to ACR) and the base rate comes from the “Average Base Payment Level from Plans to Providers” column (converted into a Medicare-equivalent rate when benchmarked to ACR).

Formula 1:

Appendix Table 1

Analysis StepCount of PreprintsFederal Spending Among Preprints (billion $)Federal Hospital Spending Among Preprints (billion $)Notes
Preprints listed on CMS’s website as of May 12, 20261,038 


All preprints pulled from CMS website987246.4202.1Some links are broken or duplicates
Preprints in time period and states570 
166.1
 
137.8Includes the preprint for each state directed payment (SDP) from January 2024 onward for the 50 states and DC
Most recent SDP submission or renewal35899.682.2Limits to the most recent preprint where the sample previous included renewals
Preprints without data quality issues35299.682.2KFF dropped preprints that were missing information about the start date, end date, spending amounts, etc.
Preprints manually reviewed and dropped (sample for previous KFF analysis)30593.178.0KFF dropped preprints from older years that were subsumed into newer preprints and those that were temporary policies started during the COVID-19 pandemic
Include hospital services13987.978.0


Preprints that require a benchmark13380.177.8Benchmarks are only required for SDPs that require managed care organizations to make payments that are on top of the negotiated rates.
Use Medicare or average commercial rates as benchmark13180.177.8


Optional Medicaid and CHIP Coverage for Lawfully Present Immigrant Children Could Mitigate Coverage Losses Due to 2025 Reconciliation Law

Authors: Carlos Cruz, Drishti Pillai, and Samantha Artiga
Published: Aug 14, 2026

Summary

Actions taken by the Trump administration and Congress will likely have major impacts on health and health care for immigrant families, including reducing the number of lawfully present immigrants eligible for federally funded health coverage under the 2025 reconciliation law. While undocumented immigrants have already been ineligible for federally funded health coverage, the law newly limits Medicaid and Children’s Health Insurance Program (CHIP), subsidized Affordable Care Act (ACA) Marketplace, and Medicare coverage to lawfully present immigrants who are lawful permanent residents (LPRs) or green card holders, certain Cuban or Haitian immigrants, and people residing in the U.S. under Compacts of Free Association (COFA). As such, many lawfully present immigrants, including humanitarian immigrants, such as refugees and asylees, will become ineligible for coverage. However, the law does not eliminate optional Medicaid and CHIP coverage under the Immigrant Children’s Health Improvement Act (ICHIA) for lawfully residing children and pregnant people. This option allows a state to cover a broader group of lawfully present immigrants who meet income and other eligibility requirements. As such, ICHIA coverage could help mitigate potential coverage losses for lawfully present immigrant children and pregnant people.

This brief provides an overview of health coverage of noncitizen children based on KFF analysis of 2024 American Community Survey (ACS) data to provide greater insight into the potential role of ICHIA coverage in limiting the law’s impact on coverage for lawfully present immigrant children. While there are few noncitizen children in the U.S. overall, their access to health coverage has important implications for their health and well-being, including their long-term health and economic stability as adults. Although states can also use ICHIA to expand coverage for lawfully present immigrant pregnant people, this analysis does not include this group since they cannot be separately identified in ACS data. Similarly, the analysis includes all noncitizen children rather than just lawfully present immigrant children, because the data do not provide information on immigration status. However, separate research suggests there are very few undocumented children in the U.S. overall. Key takeaways include the following:

  • As of April 2026, 38 states have implemented ICHIA coverage for lawfully residing immigrant children, and over nine in ten (92%) of the approximately 2.6 million noncitizen children in the U.S. live in a state with ICHIA coverage for children.
  • Noncitizen children are more likely to be uninsured than citizen children. Recent noncitizen children in the U.S. for less than five years are at the highest risk of being uninsured, with 28% lacking coverage compared to 22% of their longer-term noncitizen counterparts and 5% of citizens.
  • The uninsured rate for noncitizen children living in states that have adopted ICHIA coverage for children is lower compared to the rate for noncitizen children living in states that have not (25% vs 37%), likely reflecting a combination of ICHIA coverage and other more expansive coverage policies in these states.

Together, the data show that Medicaid, CHIP, and other public coverage help reduce uninsured rates for noncitizen children, particularly recent noncitizen children living in ICHIA states. Maintaining ICHIA coverage could help mitigate coverage losses for lawfully present immigrant children as the 2025 reconciliation law eligibility restrictions go into effect. Additionally, implementation of ICHIA coverage in the states that have not yet adopted it or that have room to expand it for either children or pregnant people could further limit coverage losses. Even with ICHIA coverage in place, outreach and communication to families and effective processes to screen individuals for eligibility under the option will be important for preventing administrative coverage losses among those eligible as new restrictions are implemented.

Medicaid and CHIP Coverage Under the ICHIA Option

Prior to the 2025 reconciliation law, undocumented immigrants were already ineligible for Medicaid, CHIP, and other federally funded coverage, and lawfully present immigrants faced eligibility restrictions for Medicaid and CHIP. In 1996, the Personal Responsibility and Work Opportunity Reconciliation Act limited Medicaid and CHIP eligibility to certain groups of lawfully present immigrants deemed to have a “qualified status” and required many of these groups to wait at least five years before they could enroll even if they met other eligibility criteria (Table 1). As such, many lawfully present immigrants faced a five-year waiting period for coverage and others remained ineligible regardless of their length of time in the country, although some groups were exempt from the five-year waiting period. Lawfully present immigrants were eligible for ACA Marketplace coverage with subsidies to offset the cost of this coverage during their five-year waiting period for Medicaid or CHIP.

Table 1: Lawfully Present Immigrants by Qualified Status
Lawfully Present Immigrants With
“Qualified Status”
Lawfully Present Immigrants Without
“Qualified Status”
• Lawful permanent resident (LPR or green card holder)
• Refugee
• Asylee
• Cuban/Haitian entrant
• Paroled into the U.S. for at least one year
• Conditional entrant granted before 1980
• Granted withholding of deportation
• Battered noncitizen, spouse, child, or parent
• Victims of trafficking and their spouse, child, sibling, or parent or individuals with pending application for a victim of trafficking visa
• Member of a federally recognized Indian tribe or American Indian born in Canada
• Citizens of the Marshall Islands, Micronesia, and Palau who are living in one of the U.S. states or territories (referred to as Compact of Free Association or COFA migrants)
• Granted Withholding of Deportation or Withholding of Removal, under the immigration laws or under the Convention against Torture (CAT)
• Individual with Non-Immigrant Status, includes worker visas, student visas, U-visa, and other visas, and citizens of Micronesia, the Marshall Islands, and Palau
• Temporary Protected Status (TPS)
• Deferred Enforced Departure (DED)
• Deferred Action Status
• Lawful Temporary Resident
• Administrative order staying removal issued by the Department of Homeland Security
• Resident of American Samoa
• Applicants for certain statuses
• People with certain statuses who have employment authorization

Since 2009, states have had the option to expand Medicaid and CHIP coverage for lawfully residing children and pregnant people under ICHIA. This option extends eligibility to lawfully residing children and/or pregnant people beyond those with “qualified status” and eliminates the five-year waiting period for coverage. As of April 2026, 38 states including DC have taken up this option for children and pregnant people or for children only and 2 states have taken it up for pregnant people only (Figure 1).Most states that have taken up ICHIA for children have taken up other coverage expansion options. These include options such as the ACA Medicaid expansion to low-income adults and fully state-funded coverage for certain groups of immigrants, such as children, regardless of immigration status (Appendix Table 1.)

Most States Have Expanded Coverage to Lawfully Residing Immigrant Children (Choropleth map)

Health Coverage Among Noncitizen Children

As of 2024, there were approximately 2.6 million noncitizen children ages 0 to 18 residing in the U.S. This includes 61% or 1.6 million who are recent noncitizen children in the U.S. for less than five years and 39% or 1 million who have been in the U.S for five or more years. This group includes both lawfully present and undocumented immigrants, although other research suggests there are very few undocumented children in the U.S. overall.

Noncitizen children are significantly more likely to be uninsured than their citizen counterparts (Figure 2). Recent noncitizen children are at the highest risk of being uninsured, with 28% lacking coverage compared to 22% of their longer-term noncitizen counterparts and 5% of citizens. The higher uninsured rate among noncitizen children reflects a lower rate of private coverage. Rates of public coverage for children are similar across citizenship status and length of time in the country. However, noncitizen children are more likely than their citizen counterparts to live in a low-income family and, therefore, are more likely to be eligible for public coverage yet enrolled at lower rates.

Noncitizen Children are More Likely to Be Uninsured Than Their Citizen Counterparts (Stacked Bars)

The uninsured rate for noncitizen children is significantly lower in states that have adopted the ICHIA option for children compared to the rate for noncitizen children in states that have not adopted this option (25% vs. 37%). This pattern holds true across both recent noncitizen children (27% vs. 35%) as well as longer-term noncitizen children (21% vs. 40%). The lower uninsured rate in these states is largely driven by higher rates of public coverage, particularly among recent noncitizen children. This likely reflects the expanded coverage to recent lawfully residing immigrant children who would otherwise be in the five-year waiting period as well as broader groups of lawfully residing immigrant children who do not have “qualified status.” Additionally, as noted, some of these states have implemented other coverage expansions for immigrant children, such as fully state-funded programs, as well as broader expansions for the low-income population, including the ACA Medicaid expansion to low-income adults, which may have spillover effects on children’s coverage. States with ICHIA coverage for children also cover a much larger number of noncitizen children than states without ICHIA, as over nine in ten (92%) of noncitizen children live in these 38 states.

Noncitizen Children in States with ICHIA Coverage Are Less Likely to be Uninsured than Those in States Without ICHIA Coverage (Stacked Bars)

ICHIA Coverage Under the 2025 Reconciliation Law

The 2025 reconciliation law limits eligibility for federally funded coverage, including Medicaid, CHIP, subsidized ACA Marketplace, and Medicare coverage, to LPRs (green card holders), certain Cuban and Haitian entrants, and people residing in the U.S. under COFA. This change eliminates eligibility for many groups of lawfully present immigrants such as refugees, U visa holders and applicants, and people with Temporary Protected Status, and is expected to lead to 1.4 million lawfully present immigrants becoming uninsured by 2034. The Medicaid and CHIP eligibility restrictions will take effect as of October 1, 2026, and are expected to lead to 100,000 individuals becoming uninsured by 2034.

The 2025 reconciliation law did not eliminate optional Medicaid and CHIP coverage for lawfully residing children and/or pregnant people under ICHIA. ICHIA coverage provides eligibility for a broader group of lawfully present immigrants in these groups who would otherwise no longer be eligible under the reconciliation law and also extends eligibility to recent immigrants who would otherwise be subject to the five-year waiting period for Medicaid and CHIP.

States could mitigate coverage losses for lawfully present immigrant children and pregnant people by maintaining or expanding ICHIA coverage. Overall, 11 states have not taken up ICHIA coverage for either children or pregnant people, 8 states have taken up the option for children but could expand it to pregnant people, and 2 states have taken up the option for pregnant people only but could expand it to children. Conversely, elimination of ICHIA coverage could exacerbate coverage losses for these groups. Some states facing budget pressures have recently cut back on state-funded coverage for immigrants. While no state has eliminated ICHIA coverage to date, states continue to face increasing budget pressures. ICHIA cannot mitigate coverage losses among non-pregnant adults who will no longer be eligible for Medicaid based on their immigration status.

Even with ICHIA coverage in place, outreach and education to families and effective eligibility screening processes will be important to prevent administrative losses among those still eligible as the reconciliation law changes are implemented. For example, as states implement new eligibility restrictions, it will be important to effectively screen people for eligibility under the ICHIA option to make sure they do not lose coverage if they are still eligible. Families may also be confused about shifting eligibility rules, which may be compounded by confusion and fears stemming from recent changes to public charge policies. Additionally, a couple of states almost inadvertently eliminated this coverage through state legislation to implement the 2025 reconciliation law, although these changes were eventually avoided. 

Methods

Data sources: This brief is based on KFF analysis of federal survey data, namely the American Community Survey 1-year Public Use Microdata Sample. The ACS is a nationally representative household survey conducted by the U.S. Census Bureau. ACS PUMS data are available on a yearly basis. State-level data on immigrant subpopulations were excluded due to sample size.

Identifying citizenship status: U.S. citizens were defined as naturalized citizens or U.S.-born citizens. Naturalized citizens are individuals who indicate becoming a U.S. citizen by naturalization. Noncitizen immigrants are individuals who say that they are not a U.S. citizen, including both lawfully present and undocumented immigrants.

Defining insurance coverage categories: Private insurance coverage included employer-sponsored and direct purchase insurance plans. Public insurance coverage included Medicare, Medicaid, and military-sponsored insurance plans.

Defining state take-up of ICHIA: Information on state take-up of ICHIA is based on KFF and Georgetown University’s 2026 Medicaid Eligibility and Enrollment Survey. For the purposes of this analysis, the 38 states that have taken up ICHIA for lawfully residing children were grouped into “States with ICHIA Coverage” for children.

Appendix Table 1: State Take-Up of Health Coverage Expansions
StateICHIA OptionACA Medicaid ExpansionFCEP OptionState-Funded Coverage
ChildrenPregnant PeopleChildren or Pregnant PeopleAdults
States That Have Adopted ICHIA Coverage for Children
ArkansasYesYesYesYesNoNo
CaliforniaYesYesYesYesYesYes
ColoradoYesYesYesYesYesYes
ConnecticutYesYesYesYesYesNo
DelawareYesYesYesNoNoNo
District of ColumbiaYesYesYesYesYesYes
FloridaYesNoNoNoNoNo
GeorgiaYesYesNoNoNoNo
HawaiiYesYesYesNoNoNo
IllinoisYesNoYesYesYesYes
IowaYesNoYesNoNoNo
KentuckyYesYesYesNoNoNo
LouisianaYesNoYesYesNoNo
MaineYesYesYesYesYesNo
MarylandYesYesYesYesNoNo
MassachusettsYesYesYesYesYesNo
MichiganYesYesYesYesNoNo
MinnesotaYesYesYesYesYesNo
MontanaYesNoYesNoNoNo
NebraskaYesYesYesYesNoNo
NevadaYesYesYesNoNoNo
New HampshireYesYesYesNoNoNo
New JerseyYesYesYesNoYesNo
New MexicoYesYesYesNoNoNo
New YorkYesYesYesYesYesYes*
North CarolinaYesYesYesNoNoNo
OhioYesYesYesNoNoNo
OregonYesNoYesYesYesYes
PennsylvaniaYesYesYesNoNoNo
Rhode IslandYesYesYesYesYesNo
South CarolinaYesYesNoNoNoNo
TexasYesNoNoYesNoNo
UtahYesNoYesNoYesNo
VermontYesYesYesNoYesNo
VirginiaYesYesYesYesNoNo
WashingtonYesYesYesYesYesYes
West VirginiaYesYesYesNoNoNo
WisconsinYesYesNoYesNoNo
States that Have Not Adopted ICHIA Coverage for Children
AlabamaNoNoNoYesNoNo
AlaskaNoNoYesNoNoNo
ArizonaNoNoYesNoNoNo
IdahoNoNoYesNoNoNo
IndianaNoNoYesNoNoNo
KansasNoNoNoNoNoNo
MississippiNoNoNoNoNoNo
MissouriNoNoYesYesNoNo
North DakotaNoYesYesNoNoNo
OklahomaNoNoYesYesNoNo
South DakotaNoNoYesYesNoNo
TennesseeNoNoNoYesNoNo
WyomingNoYesNoNoNoNo
Note: "ICHIA Option" for children or pregnant people includes states that implement ICHIA for these populations as of January 2026. "Medicaid Expansion" includes states that have adopted the Affordable Care Act’s (ACA) expanded Medicaid coverage to nearly all adults with incomes up to 138% of the Federal Poverty Level as of May 2026. "FCEP Option" includes states that adopted the CHIP From-Conception-to-End-of-Pregnancy (FCEP) option. "State-Funded" includes states that provide any state-funded health coverage to income-eligible adults or children regardless of immigration status as of April 2026. State-funded coverage for adults in New York is limited to individuals 65 or older.
Source: KFF/Georgetown University, 2026 Medicaid Eligibility and Enrollment Survey (April 2026); KFF, “Status of State Medicaid Expansion Decisions” (May 2026); KFF, “Medicaid and CHIP Income Eligibility Limits for Pregnant Women as a Percent of the Federal Poverty Level” (January 2026); KFF, “State Health Coverage for Immigrants and Implications for Health Coverage and Care” (May 2026).

VOLUME 52

Many Adults Are Unaware of the Abortion Pill’s Safety and Prevalence as Misleading Claims Link the Medication to Wastewater Contamination


Highlights

Recently released findings from KFF’s July Health Tracking Poll show that much of the public is unsure of the abortion pill mifepristone’s safety, and most lack awareness that most abortions in the U.S. are performed via medications. These findings come as some groups opposed to abortion are citing a misleading paper in an effort to classify mifepristone as a water contaminant, despite criticism of the paper’s methodology and a lack of evidence demonstrating the drug poses an environmental risk.


The latest KFF Health Tracking Poll examines the public’s knowledge and views of mifepristone – or medication abortion – amid an ongoing FDA re-review of the medication’s safety.

Much of the public is unaware of mifepristone’s long-standing safety record. While larger shares of adults say medication abortion is safe (44%) than say it is unsafe (15%) when taken as directed by a health care provider, about four in ten (41%) say they are unsure. This uncertainty is higher among Black women, with half (51%) saying they are unsure whether abortion pills are safe. Among women of reproductive age – or those ages 18-49 – roughly half (52%) view the abortion pills as safe while three in ten are not sure.

Republicans (50%) and independents (42%) are most likely to be uncertain about mifepristone’s safety, while a majority of Democrats (61%) view the medication as safe.

Stacked bar chart showing share of adults who believe abortion bills are very safe, somewhat safe, somewhat unsafe, very unsafe, or are unsure of the correct answer. Results shown by total, women of reproductive age, and party.

In addition to the lack of awareness of mifepristone’s safety record, just about a quarter (26%) of the public is aware that most abortions in the U.S. are performed via abortion pills, while 26% incorrectly say most abortions are performed via medical procedure and about half of the public (48%) are unsure. Larger shares of Democrats, independents, women of reproductive age, and those who identify as “pro-choice” correctly say that most U.S. abortions are performed with abortion pills, though uncertainty is still high among these groups, with roughly half saying they are unsure. 

Stacked bar chart showing share of adults who believe most abortions in the United States are done using abortion pills, a medical procedure, or are unsure of the correct answer. Results shown by total, women of reproductive age, party, and view on abortion.

As the FDA undertakes a re-evaluation of mifepristone’s safety, slightly more than half (54%) of the public say they have little to no confidence in the FDA to make decisions based on science when it comes to reviewing the drug’s safety. This lack of confidence is shared among roughly half of Democrats (47%) and Republicans (53%), while nearly six in ten (57%) independents lack confidence in the agency in this regard. These findings are in line with KFF’s past health information and trust polling, which has found that fewer than half of the public and partisans express confidence in federal health agencies to carry out core responsibilities, such as acting independently or making decisions based on science rather than personal views of officials. Trust in federal agencies such as the FDA and CDC as health information sources declined precipitously after the onset of the COVID-19 pandemic.


What We’re Watching

Misleading Wastewater Claims Cited in Effort to Classify Mifepristone as a Contaminant

A paper purporting to show mifepristone contaminating wastewater in three U.S. cities is being cited by an activist group opposed to abortion as the group attempts to persuade the Environmental Protection Agency (EPA) to classify the drug as a water contaminant and to push the Food and Drug Administration (FDA) to restrict or pull it from the market.

The paper was posted as a preprint in a journal run by physicians who oppose abortion. Environmental health scientists, including a former scientist at the EPA’s Office of Water, have said that it uses a testing method that does not distinguish between compounds that interact with progesterone receptors. Because of this limitation, the paper cannot accurately distinguish mifepristone from other chemicals, like bisphenol A (BPA), which is found in many plastics. An FDA environmental assessment of mifepristone conducted during the drug’s approval process estimated its environmental concentration at less than one part per billion, a level that the agency described as a likely overestimate and still too low to affect standard test organisms.

Using environmental claims to call for new restrictions on access to mifepristone is among the latest efforts in ongoing attempts to portray the drug as unsafe, despite those claims not being supported by evidence. Mifepristone’s safety has been extensively studied, with serious adverse events occurring in fewer than 0.5% of patients. Still, though, a report published by a group opposed to abortion last year that claimed to show a much higher rate of adverse events is still being cited in legislative challenges to mifepristone access, despite that report similarly being met with criticism over its methodology.


AI & Emerging Technology

AI-Generated “Doctors” and Deepfakes of Real Physicians Are Being Used to Sell Supplements Online

A series of recent investigations have found networks of AI-generated “doctors” across social media platforms promoting supplements and unproven treatments as supposed “miracle cures” for a range of conditions. A New York Times video investigation found hundreds of entirely AI-generated wellness influencers and doctors on social media, not based on any real person and with fabricated names, faces, and credentials. These videos often target older women with before-and-after transformation videos and fake diplomas displayed in fake offices. In Spain, the fact-checking organization Maldita.es found more than 1,000 AI-generated “doctor” channels on YouTube and 25 similar accounts on Instagram, often promoting the same types of unproven cures.

One 71-year-old woman interviewed by the Times said she began taking a supplement after seeing an AI-generated ad for a product she was led to believe could help treat symptoms of an autoimmune disease. The product was later recalled after being linked to salmonella contamination. In other cases, ads made dangerous health claims, including that a supplement could be more effective in treating Stage 3 kidney disease than medication. In addition to these synthetic personas, deepfake videos of actual, named physicians have also been used to promote unproven treatments.

Medical Organizations Call for Legislative Protections Against AI Physician Deepfakes

Legislative efforts to prevent such impersonation have been introduced at both the federal and state level, with the American Medical Association (AMA) endorsing a bill that would hold individuals or platforms liable for distributing an unauthorized digital replica of a person’s voice or likeness. In California, a bill supported by the California Medical Association would require ads using an AI-generated or altered likeness of a real person to include a clear disclosure that the content was AI-generated.

Social Media Platform Enforcement of AI-Generated Content Remains Inconsistent

Social media platforms, including Meta and TikTok, have said that they label AI-generated content and remove ads making misleading health claims, but the Times investigation found uneven enforcement. Maldita.es found some flagged Instagram accounts carrying the platform’s blue verification badge, typically reserved for confirming a user’s identity. A separate audit that posted more than 200 AI-generated images and videos across five platforms similarly found inconsistent labeling, with Instagram correctly labeling only 15 of 105 synthetic images posted to the platform, while TikTok labeled about a third.

Why This Matters

AI-generated videos that imitate the credibility of real or fabricated health professionals may exploit both the public’s high trust in doctors as purveyors of health information and the confidence that some social media users have in their ability to discern false health claims. June KFF polling found that fewer than four in ten (36%) adults who seek health information on social media follow up with a doctor or health professional at least most of the time to verify what they’ve seen, and a majority of those who use social media for health (65%) say they’re confident in their ability to tell whether health information posted on these platforms is true or false.

About The Health Information and Trust Initiative: the Health Information and Trust Initiative is a KFF program aimed at tracking health misinformation in the U.S., analyzing its impact on the American people, and mobilizing media to address the problem. Our goal is to be of service to everyone working on health misinformation, strengthen efforts to counter misinformation, and build trust. 


View all KFF Monitors

The Monitor is a report from KFF’s Health Information and Trust initiative that focuses on recent developments in health information. It’s free and published twice a month.

Sign up to receive KFF Monitor
email updates


Support for the Health Information and Trust initiative is provided by the Robert Wood Johnson Foundation (RWJF). The views expressed do not necessarily reflect the views of RWJF and KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities. The data shared in the Monitor is sourced through media monitoring research conducted by KFF.

Prior Authorization Metrics Provide New Insights into Insurer Practices, but Gaps Remain

Published: Aug 13, 2026

The use of prior authorization by health insurers has come under increased scrutiny in recent years, as nearly 7 in 10 insured adults say prior authorization is a burden when it comes to getting health care. Health insurers use prior authorization to reduce the use of low-value or unnecessary care, and in the complex and fragmented U.S. health care system is one of the primary tools used to restrain costs. Nevertheless, this practice may result in delays or denials in receiving necessary care, as well as administrative burdens for patients and providers.

In 2024, the Centers for Medicare and Medicaid Services (CMS) published a final rule (“2024 regulation”) aimed at streamlining and automating the prior authorization process for almost all insurance programs it oversees: Medicare Advantage, Medicaid and CHIP fee-for-service and managed care plans, and Affordable Care Act (ACA) Marketplaces on the federally facilitated exchanges (HealthCare.gov). As part of these requirements, every year, payers in these programs are now required to publicly post on their websites specified prior authorization metrics, including approval and denial rates and response times, aggregated for all medical items and services (excluding prescription drugs) for the previous calendar year.

Insurers were required to post the first year of data, for the 2025 calendar year, by March 31, 2026. KFF collected and analyzed these metrics from the largest insurers in most market segments for which reporting is required, including Medicare Advantage, Medicaid managed care, and the Affordable Care Act (ACA) federally facilitated Marketplace. This issue brief summarizes the data by market segment and insurer and discusses the challenges interpreting the data as well as emerging policy changes that may address some of them.

  • Medicare Advantage insurers denied 12% of standard prior authorization requests, Medicaid managed care insurers denied 14%, and ACA Marketplace insurers denied 18%. Denial rates for expedited requests were slightly lower. However, the aggregated approval statistics do not allow for further analysis into which services are being denied.
  • Prior authorization denials are rarely appealed, but when they are, a considerable share are overturned. Sixty-seven percent of prior authorization denials were overturned upon appeal in Medicare Advantage, 47% were overturned upon appeal in Medicaid managed care, and 43% were overturned in the ACA federally facilitated Marketplace.
  • Median response times in all markets were about 1 day for standard prior authorization requests, and about half a day for expedited prior authorization requests for Medicare Advantage, and approximately 1 day for Medicaid managed care and the ACA Marketplace. Insurers are not required to report response time ranges or differences by service category.  
  • Despite the regulatory intent to make insurer prior authorization practices more transparent, difficulty locating and interpreting metrics on insurer websites and gaps in how (e.g., a standardized template that insurers are required to use) and what metrics (e.g., denominators and breakouts by service category) must be reported limit the usability of this information directly by the public.

Overview of the 2024 Regulation’s Prior Authorization Metrics Requirements

The regulation states that the overall goal of this public reporting requirement is to promote “accountability for payer prior authorization practices” and envisions consumers using the data when shopping for health insurance. The regulation requires payers to which it applies — Medicare Advantage organizations, Medicaid and CHIP fee-for-service and managed care plans, and insurers on the ACA federally facilitated Marketplace (FFM), hereafter collectively referred to as insurers — to provide a list of all medical items and services that require prior authorization (excluding prescription drugs) and report the following metrics aggregated for all medical items and services (excluding prescription drugs) for each line of business:

  • Percentage of standard and expedited prior authorization requests that were approved and denied
  • Percentage of standard prior authorization requests that were approved after appeal (i.e., overturned denials)
  • Percentage of all prior authorization requests where review timeframes were extended and the request was approved
  • Average (i.e., mean) and median timeframes between submission of a prior authorization request and determination for standard and expedited prior authorization requests

Additional metrics were made optional, including:

  • Percentage of expedited prior authorization requests that were approved after appeal
  • Percentage of prior authorization requests where decision timeframes were extended and then the requests were approved, broken out by standard and expedited requests
  • Percentage of prior authorization requests approved within 7 days for standard requests and 72 hours for expedited requests
  • Numeric counts for metrics, including total number of requests and appeals received

Describing “Standard” and “Expedited” Prior Authorization Requests

The 2024 regulation refers to “standard” prior authorization as non-expedited, non-urgent requests and to ‘‘expedited’’ prior authorization as urgent requests. Other federal regulations generally base these terms on whether the standard timeframe could seriously jeopardize an enrollee’s life, health, or ability to regain maximum function. In 2025, the year for which prior authorization metrics are reported, insurers were required to send a determination for standard requests within 14 calendar days for Medicare Advantage and Medicaid managed care and within 15 days for the ACA Marketplace. Determinations for expedited requests had to be sent within 72 hours for insurers in all three markets.1

The 2024 regulation introduced new prior authorization reporting requirements for some business segments and expanded them for others.

  • For Medicare Advantage, insurers have been required to report information about the use of prior authorization – including the number of requests, denials, and appeals – for several years, with data available to researchers for 2019 through 2024. Data on the share of prior authorizations approved, denied, and approved upon appeal are largely duplicative of the information Medicare Advantage insurers already report. The regulation adds new requirements to provide information on response times and to report metrics separately for standard and expedited requests.
  • For Medicaid and the ACA FFM, uniform federal reporting requirements for prior authorization are new,2 though an existing patchwork of state laws and regulations has required some insurers to report certain prior authorization data at the state level.

Prior Authorization Metrics

Data collected for this analysis represent the largest insurers in each business segment — those with at least 2.5% market share in each of their respective markets: Medicare Advantage, Medicaid managed care, and the ACA FFM.3,4 In total, this analysis includes data from 14 unique insurers, representing 25 million Medicare Advantage enrollees (69% of all enrollment), more than 35 million Medicaid managed care organization (MCO) enrollees (54% of all enrollment), and nearly 11 million enrollees in the ACA FFM (hereafter referred to as the ACA Marketplace for simplicity), which included 28 states in 2025 (74% of all enrollment in FFM states). KFF weighted the data by enrollment within each market segment. See the Methodology section for more details.

This analysis includes the share of standard and expedited prior authorization requests that were approved and denied, the share of standard prior authorization requests that were approved after appeal, and the median response times for standard and expedited prior authorization requests. We do not report the share of prior authorization requests approved after extension because some insurers reported the data only for standard requests, while others reported data separately for standard and expedited. Optional metrics are not included because they were not consistently reported by insurers.

Approval and Denial Rates

Across market segments, insurers denied between 12% and 18% of standard prior authorization requests in 2025. On average, 12% of standard prior authorization requests and 10% of expedited prior authorization requests were denied in Medicare Advantage; 14% of standard requests and 12% of expedited requests were denied in Medicaid managed care; and 18% of standard prior authorization requests and 16% of expedited prior authorization requests were denied in the ACA Marketplace (Figure 1). Across all markets, the share of standard prior authorization requests that were denied was similar to or slightly higher than the share of expedited prior authorization requests that were denied.

Figure 1

Prior authorization denial rates varied widely across the largest insurers (Figure 2).

Medicare Advantage: Among the six Medicare Advantage insurers examined, the share of standard prior authorization requests that were denied ranged from 5% (Elevance) to 17% (UnitedHealth Group), and the share of expedited requests that were denied ranged from 3% (Elevance) to 13% (Centene). UnitedHealth Group, Centene, Kaiser Permanente, and Elevance all had somewhat higher denial rates for standard requests than expedited requests, while CVS and Humana had higher denial rates for expedited requests than standard requests. These are similar to the overall denial rates found in a previous KFF analysis across Medicare Advantage insurers.5

Medicaid Managed Care: Among the eight Medicaid managed care insurers examined, the share of standardprior authorization requests that were denied ranged from 2% (L.A. Care Health Plan) to 23% (Independence Health Group). For expedited requests, denial rates ranged from 4% (L.A. Care Health Plan) to 21% (CareSource). Three insurers (Centene, Independence Health Group, and UnitedHealth Group) reported higher denial rates for standard requests compared to expedited requests, while three insurers (CVS Health, CareSource, and L.A. Care Health Plan) reported slightly higher denial rates for expedited requests.6

ACA Marketplace: Among the eight ACA Marketplace insurers included in this analysis, the share of standard prior authorization requests that were denied ranged from an average of 3% (GuideWell) to 25% (Centene). Denial rates for expedited requests ranged from 3% (GuideWell) to 23% (Centene). Four insurers (Centene, UnitedHealth Group, Blue Cross and Blue Shield of North Carolina, and Molina) reported higher denial rates for standard requests compared to expedited requests, while two insurers (Elevance and Health Care Service Corporation) reported higher denial rates for expedited requests.7 The remaining two insurers (Oscar and GuideWell) in this analysis had virtually the same rates of denials for both standard and expedited requests.

Market segments inherently have many differences, and the share of prior authorization requests denied also varied for the same insurer participating in multiple markets. For example, UnitedHealth denied 17% of standard requests in Medicare Advantage, 11% in Medicaid managed care, and 21% in the ACA Marketplace.

Figure 2

Appeals Data

Insurers overturned a considerable share of denials upon appeal, with variation by market. Although enrollees or their providers can appeal denied prior authorization requests, research shows that denials are rarely appealed in Medicare Advantage, Medicaid MCOs, or the ACA Marketplace. However, the prior authorization data demonstrate that when denials are appealed, a considerable share are overturned.

The share of standard prior authorization requests initially denied that were then overturned upon appeal8 (referred to in the CMS template as “Requests Approved After Appeal”) was 67% for Medicare Advantage, 47% for Medicaid managed care, and 43% in the ACA Marketplace (Figure 3). We do not present appeals data for expedited requests because that metric is optional, and most insurers did not provide this information. High overturn rates could raise questions about whether the initial request should have been approved or could indicate that the initial request was missing the required documentation to justify the service. Either way, the appeals process can be complicated and time-consuming for providers and patients.

In Medicare Advantage, if the plan upholds its original denial, the case is automatically sent to an independent review entity. In contrast, there is no automatic external medical review of upheld denials in Medicaid managed care and the ACA Marketplace. HHS OIG has suggested that the presence of automatic, independent review could incentivize Medicare Advantage plans to closely review their denials at the first level of appeal and may help explain higher appeal overturn rates in Medicare Advantage compared to Medicaid managed care and the ACA Marketplace.

Stacked bar chart showing the share of appealed standard prior authorization denials that were overturned or upheld in Medicare Advantage, Medicaid managed care and the ACA Marketplace. The chart shows that insurers reversed a substantial share of denied requests when patients or providers appealed, though the likelihood of reversal varied by market segment. In Medicare Advantage, 67% of appealed denials were overturned and 33% were upheld. In Medicaid managed care, appeals were nearly evenly split, with 47% overturned and 53% upheld. In the ACA Marketplace, 43% of appealed denials were overturned and 57% were upheld. Overall, the figure shows that many denials are eventually reversed on appeal, particularly in Medicare Advantage, suggesting that initial prior authorization decisions are not always final.

Appealed prior authorization denials were overturned more often by some large insurers than others (Figure 4).

Medicare Advantage: Across the six largest Medicare Advantage insurers, the share of denied standard prior authorization requests that were approved varied substantially. Denials were overturned upon appeal more than 90% of the time by Centene, while Kaiser Permanente overturned denials upon appeal 40% of the time.

Medicaid Managed Care: Among the Medicaid managed care insurers examined, UnitedHealth Group overturned 81% of denials upon appeal. The remaining insurers overturned between 22% (CVS) and 48% (Molina) of denials upon appeal. (One Medicaid managed care insurer included in this analysis (L.A. Care Health Plan) did not report overturned prior authorization denials as a percentage of standard prior authorization requests that were appealed; therefore, its appeals data are not included here.)

ACA Marketplace: On average, Health Care Service Corporation overturned just 16% of denials upon appeal, while Centene overturned just over half (54%) of denials upon appeal. Six of the eight large insurers reported overturning denials upon appeal less than half the time.

Figure 4

Median Response Times

Median response times for prior authorization determinations were about 1 day for standard requests, with slightly more variation for expedited requests (Figure 5).

The median time between the submission of a prior authorization request and the determination by the insurer, or response time, for standard requests was about 1 day for Medicare Advantage, Medicaid managed care, and the ACA Marketplace (0.9 days or just under 22 hours), substantially less than the federally required maximum time permitted for standard requests.9 The median response time for expedited requests was about half a day (0.4 days or just under 10 hours) for Medicare Advantage, just under 1 day (0.8 days or approximately 19 hours) for Medicaid managed care, and 1 day for the ACA Marketplace. Federal regulations in 2025 required insurers to send a determination for standard requests within 14 calendar days for Medicare Advantage and Medicaid managed care and within 15 days for the ACA Marketplace. Determinations for expedited requests had to be sent within 72 hours for insurers in all three markets.10

Grouped bar chart comparing median prior authorization response times for standard and expedited requests across Medicare Advantage, Medicaid managed care and the ACA Marketplace. The chart shows that insurers typically made prior authorization decisions within about one day regardless of market segment. Median response times for standard requests were 1 day in Medicare Advantage and Medicaid managed care and 0.9 days in the ACA Marketplace. Expedited requests were decided even more quickly in Medicare Advantage, with a median response time of 0.4 days, while response times were 0.8 days in Medicaid managed care and 1 day in the ACA Marketplace. Overall, the figure shows relatively fast prior authorization decision-making across markets, with little variation in standard requests and somewhat greater variation in expedited requests.

Median response times likely reflect (at least in part) the increasing use of technology in the prior authorization process, such as artificial intelligence and electronic prior authorization systems. Still, nearly one-quarter (24%) of insured adults reported in a July 2025 KFF poll that their health insurance company had delayed their ability to get a requested health care service, treatment, or medication in the past two years.And other research and media reports demonstrate that some patients experience much longer response times, sometimes with serious health consequences. In addition to the 2024 regulation’s provisions aimed at streamlining and automating the prior authorization process, in June 2025, a group of health insurers voluntarily pledged to expand real-time responses for prior authorization approvals by 2027.

Median response times for prior authorization determinations varied somewhat among large insurers (Figure 6).

Medicare Advantage: The median response time for standard requests varied from less than 1 day (CVS, Humana, and Kaiser Permanente) to 2 days (Centene). Across the six insurers examined, the response times for expedited requests were similar or slightly shorter than the response times for standard requests.

Medicaid Managed Care: The median response time for standard prior authorization requests varied from 1 day (Centene, Elevance, and Molina) to 4 days (CareSource). Elevance had the same median response time for standard and expedited requests, while the other insurers reported shorter response times for expedited requests.

ACA Marketplace: Among the eight large insurers included in this analysis, median response times for standard requests ranged from less than 1 day (UnitedHealth Group, GuideWell, and Health Care Service Corporation) to 4 days (Molina). All but one insurer reported similar or shorter median response times for expedited requests than standard requests.

Figure 6

Challenges for Consumers Accessing and Interpreting Prior Authorization Data

Uniform federal reporting requirements represent a step toward better understanding insurer prior authorization metrics across insurance markets. While the data provide new insights, particularly for Medicaid managed care and the ACA Marketplace insurers, gaps remain. Although a target audience of prior authorization reporting is consumers, those who do not have a deep understanding of health insurance terminology and concepts may struggle to interpret these reports. In previous KFF research, one-quarter of insured adults reported difficulty understanding specific terms their health insurer uses. Difficulty locating metrics on insurer websites, an absence of more detailed data, and unclear reporting standards could additionally pose challenges for consumers wishing to use the data directly to compare health insurers, as envisioned in the 2024 regulation. However, intermediaries may aggregate and explain the data to make it more accessible for consumers.

Insurers are not required to report the number of prior authorization requests for each metric (only percentages), which limits the ability to make useful comparisons and gauge the scale of requests, denials, and approvals behind reported percentages. For instance, a low denial rate could translate into a large number of denials if the insurer received a substantial number of prior authorization requests. Conversely, a high denial rate might be seen with a relatively low number of prior authorization requests if many of those requests were denied (which could indicate the prior authorization process is better tailored, rather than a concerning number of denials). In a previous KFF analysis of the use of prior authorization in Medicare Advantage, for example, the number of prior authorization determinations per enrollee was inversely related to the share of requests that were denied (i.e., insurers with more prior authorization requests denied a smaller share of the requests than those with fewer requests). As a result, the absolute number of denied prior authorization requests per enrollee was similar across insurers with different denial rates.

Numeric counts would provide more context for understanding whether an apparently high or low denial rate reflects a meaningful volume of prior authorization requests. Additionally, they are also necessary to distinguish a true zero from missing data or inapplicable statistics. For example, the “Approved upon appeal” metric does not include the number of appeals an insurer received. Insurers that report 0% of appeals were approved are not required to indicate whether they received no appeals or that none of the appeals were approved. Furthermore, insurers were not required to report the appeal outcome by service or the reason(s) for the decision, making it difficult to interpret differences across and within markets.

Making comparisons between insurers also requires an understanding of policy nuances.  An insurer might have a high prior authorization approval rate because there are many services requiring prior authorization that are almost always approved. Some insurers exempt providers from at least some prior authorization requirements if they consistently have a high prior authorization approval rate (e.g., 90%), known as “gold card” programs. These programs can further complicate comparisons, as the approval rate no longer reflects the entirety of the procedures that might otherwise have required prior authorization. Insurers that rely heavily on gold carding may, in turn, report lower approval rates: since providers that are most clinically compliant are exempt from prior authorization, reported statistics from these insurers include only providers that may inherently have lower approval rates.

Comparisons between issuers are also challenging because of inconsistencies in how metrics are reported. Although CMS published an example template for reporting the prior authorization metrics, its use by insurers is not mandatory, and most insurers used different formats, which could make comparing metrics across insurers burdensome for the public. Some inconsistencies in reporting level could make comparisons difficult. For example, some ACA Marketplace insurers reported prior authorization metrics at the national level, as opposed to separating their reporting by state, so it is not possible to understand geographic variation in prior authorization practices from the same insurer. A national average denial rate for one insurer may or may not reflect the insurer’s denial rate in the state where the consumer lives.

Response times are difficult to interpret. Comparing response timeframes by type of request can provide some insight into the extent to which insurers are meeting the regulatory timeframe requirements. However, insurers are only required to report median and average response times, which limits the ability to determine how often decisions exceed those timeframes. Also, without a required reporting unit, some insurers reported time in hours, while others used days or fractional days. Although median response times across all three markets were typically well below the required maximums, additional information — such as optional metrics on the percentage of requests approved or denied within the required timeframe and ranges of response times — would allow for a more complete picture of how quickly prior authorization decisions are made and how frequently decision times exceed the required timeframes. Additionally, consumers may not always understand how to interpret the median – that is, by definition, half of the prior authorization requests exceed the median time reported.

Comparing insurers across lines of business requires consideration of differences between enrollee populations. Case mix (how sick the enrollee population is) and service mix (which services are most commonly provided for enrollees) likely vary substantially between lines of business, and potentially between insurers. For example, the older Medicare Advantage population likely differs substantially from the general population covered by ACA Marketplaces and the higher-need populations of Medicaid. If denial rates vary by service type and the services for which denials are more common comprise a larger share of prior authorization requests in a given business segment, the higher denial rate would reflect that difference in service use. However, without more detailed information, it is not possible to identify what is driving the differences.

In July 2026, CMS published an updated metrics reporting overview and template for insurers with changes that address some of the gaps addressed above for the 2027 reporting period. It specifies that posting metrics in locations on insurers’ websites that cannot be reached through ordinary navigation is not considered to meet the regulation’s requirement that the information be “publicly accessible.” While still not required, the updated overview does stress that the numerators and denominators specified in the template are “expected.” It notes that median determination response times that are less than one day must be reported in hours, not rounded to “0 days.” It also recommends that insurers identify and explain in their report any data quality issues or concerns.

In addition, the 2026 CMS Interoperability Standards and Prior Authorization for Drugs proposed rule (“2026 proposed rule”) attempts to address some of the data gaps in the 2024 regulation by expanding the prior authorization data that must be publicly reported. The proposed rule would require the same CMS-regulated insurers to publish new metrics for non-drug items and services (e.g., for both standard and expedited prior authorization requests, the number and percentage of requests that remain denied after appeal), as well as the numeric counts for both the new and existing metrics. Also, while CMS currently provides suggested denominators (or universe of prior authorization determinations to include), the proposed rule would standardize the denominators that insurers must use when calculating different metrics. Together, these changes would provide more insight into prior authorization requests, denials, and appeals; make the data easier to interpret; and improve the ability to make comparisons across insurers. More detailed prior authorization metrics could help assess whether initiatives to improve the prior authorization process more broadly, such as the voluntary commitments made by several insurers in June 2025, are leading to meaningful change. However, the proposed rule does not include a requirement that insurers report prior authorization metrics by service category.

Another significant proposed change would require insurers to report prior authorization metrics for prescription drugs, separate from non-drug items and services, for both standard and expedited requests. (This requirement does not apply to insurers offering Medicare Part D prescription drug plans, where separate reporting requirements for coverage determinations already apply.)

There are additional emerging federal and state data reporting policies that are market-specific:

Medicare Advantage

CMS has announced a pilot program where Medicare Advantage insurers can voluntarily submit more detailed prior authorization data, including data for specific service categories. The Trump administration has indicated that it intends to make more detailed reporting mandatory starting with the 2027 plan year. While that may help understand the impact of prior authorization in Medicare Advantage, the data will not be available for several years.

Federal legislation entitled “Improving Seniors’ Timely Access to Care Act of 2025” aims to improve prior authorization in Medicare Advantage. The bill would require Medicare Advantage plans to report certain prior authorization metrics annually to the Secretary of Health and Human Services, who would publish them on a public website. Some required metrics are similar to those required by CMS under the 2024 regulation, but the bill would also require plans to report the percentage and number of specified requests denied or approved during the previous plan year through the use of technology (e.g., artificial intelligence technology).

Medicaid Managed Care

Beginning July 2026, CMS requires states to collect and report prior authorization metrics for Medicaid managed care plans in Managed Care Program Annual Reports (MCPARs) submitted to CMS. In addition to the metrics required by the 2024 regulation, states are required to include the total number of standard and expedited prior authorization requests received. CMS makes MCPARs publicly available on Medicaid.gov, which may make data easier to locate in the future, though there will be a lag between state submission and CMS public posting.

The 2026 proposed rule would align prior authorization metric reporting for Medicaid and CHIP managed care with contract rating periods (which vary across states) and would require Medicaid and CHIP managed care plans to publicly post metrics no later than 90 days after each rating period ends. The rule would also require plans to report metrics by program (defined by a specified set of benefits and eligibility criteria identified in managed care plan contracts), as well as by plan. This proposal aligns with MCPAR reporting requirements and could provide more meaningful information on prior authorization performance by plan and program than aggregate information across programs within a state.

Private Insurance Market

Federal efforts to increase transparency into prior authorization practices in commercial coverage have so far been limited to ACA plans on the FFM. There is no publicly available prior authorization data for self-funded plans sponsored by private employers, which cover the majority of workers with employer-sponsored health insurance. Some states have taken action to increase transparency into prior authorization practices, including by collecting more granular prior authorization data from state-regulated insurers than the 2024 federal regulation requires and using the data to inform future actions aimed at curbing certain insurer practices.

For example, in 2025, Massachusetts conducted a special examination requiring insurers offering fully insured health plans in the state’s private insurance market to submit detailed prior authorization data (including numeric counts and prescription drugs) broken out by service category. The state published an analysis of the data in 2026, noting that it intended to use the data to inform future regulatory guidance. Following this examination, the state updated its insurance regulations to prohibit prior authorization requirements for a wide variety of services provided in-network, including some identified in the state’s analysis as having the most prior authorization requests and high approval rates, such as radiology (for enrollees with cancer) and physical, occupational, and speech therapy.

Similarly, in 2025, Iowa enacted a law requiring state-regulated insurers to submit certain prior authorization data to the state annually, which will be made available to the public, and requiring utilization review organizations to eliminate prior authorization requirements for health care services that meet certain criteria.

Going forward, more states may build upon the federal requirements by requiring insurers in their state to provide more detailed information about prior authorization practices and use that information to address the scope of prior authorization requirements.

This analysis includes data collected from the websites of Medicare Advantage, Medicaid managed care, and ACA federally facilitated Marketplace (FFM) insurers that each had at least 2.5% market share of enrollment in their respective market segments. In total, we collected data from 14 unique insurers in these markets, representing approximately 71 million enrollees. See Appendix Table 1 for more details.

We reported prior authorization metrics at the parent company level. Subsidiary insurers may have a different name from the parent company, and the parent company may own more than one insurer. For ease of reading, we refer to the parent company as the “insurer” in this analysis.

Medicare Advantage

Public reports were collected for Medicare Advantage insurers enrolling at least 2.5% of all Medicare Advantage enrollees in 2025. Altogether, these insurers comprised 72% of Medicare Advantage enrollment in 2025. In some cases, reports could not be located, and so the data included in this analysis reflects information provided for Medicare Advantage contracts covering 69% (25 million) of Medicare Advantage enrollees in 2025. Specifically, reports covering at least 95% of enrollment were identified for each insurer included in the analysis, with the exception of Elevance-sponsored plans, where reports covering 83% of enrollment were identified. Medicare Advantage organizations are required to report metrics at the contract level. CMS December 2025 enrollment was used to weight contract-level data when aggregating to the insurer and total market level.

Medicaid Managed Care

Public reports were collected for Medicaid MCO insurers enrolling at least 2.5% of all Medicaid MCO enrollees as of July 2024 (the latest available national Medicaid managed care enrollment data). Reports for limited benefit prepaid ambulatory health plans (PAHPs) and prepaid inpatient health plans (PIHPs) were not included. Altogether, these insurers comprised 57% of Medicaid MCOs as of July 2024. In some cases, reports could not be located, and so the data included in this analysis reflects information provided for Medicaid MCO contracts covering 54% (nearly 36 million) of Medicaid MCO enrollees as of July 2024. Specifically, reports covering at least 92% of enrollment were identified for each insurer included in the analysis, with the exception of Molina and Independence Health Group plans, where reports covering 87% and 84% of enrollment, respectively, were identified. CMS July 2024 enrollment was used to weight plan-level data when aggregating to the insurer and total market level.

Although the 2024 regulations require Medicaid and CHIP fee-for-service (FFS) programs and CHIP managed care plans to publicly report prior authorization metrics, these entities are not included in this analysis because reports were difficult to locate and comprehensive national plan-level enrollment data are not available for CHIP managed care. Additionally, the populations and services covered under FFS vary substantially across states, limiting comparability.

ACA Marketplace

We searched for public reports for the nine ACA Marketplace insurers with at least 2.5% market share in the 28 states that used the FFM (HealthCare.gov) in 2025. (Federal reporting requirements do not extend to states that operate their own Marketplaces, including state-based Marketplaces that use the HealthCare.gov platform). Prior authorization metrics could not be located for one of these insurers (CVS, which had 5% market share). UnitedHealth Group, which reported prior authorization data at the state level, did not include data for its plans sold in Oklahoma (less than 1% of its enrollment). Altogether, the data in this analysis reflect information provided for Marketplace insurers covering 74% (10.8 million) of ACA FFM enrollees in 2025.

Marketplace insurers are required to report metrics at the issuer level. Some insurers broke out their prior authorization metrics by state, while others provided national averages. ACA Marketplace enrollment was obtained from Mark Farrah Associates Health Coverage Portal, including mapping insurers to parent companies. To weight insurer-level data to the total market, enrollment was first filtered to FFM states and then aggregated to parent company.

Due to the large number of smaller insurers in the ACA Marketplace, relative to Medicare Advantage and Medicaid managed care, we also collected and analyzed data for ACA FFM insurers that had at least 1% market share in 2025, compiled in Table 2 of the Appendix. For consistency across market segments, however, only data from insurers with at least 2.5% market share were included in the overall analysis.

Table showing enrollment and market share for major Medicare Advantage insurers and the share of enrollment included in KFF’s prior authorization analysis. UnitedHealth Group is the largest Medicare Advantage insurer, with 10.3 million enrollees and a 28.8% market share, followed by Humana at 16.3% and CVS at 11.8%. The analysis includes data representing 24.7 million enrollees, or 69.0% of the Medicare Advantage market. The included insurers account for nearly all of the enrollment attributed to UnitedHealth Group, Humana, CVS and Kaiser Permanente, while included enrollment is somewhat lower for Elevance and Centene. Overall, the table shows that the prior authorization analysis covers insurers representing more than two-thirds of total Medicare Advantage enrollment.
Table comparing reported prior authorization metrics for ACA Marketplace insurers with at least a 1% market share in HealthCare.gov states. The table presents approval rates, denial rates, appeal overturn rates and median response times for standard and expedited prior authorization requests. Across insurers, standard request approval rates range from 73% to 97%, while denial rates range from 3% to 27%. The share of denied requests approved on appeal ranges from 16% to 61%, indicating substantial variation in appeal outcomes. Median response times for standard requests range from 0 to 4 days. Expedited requests generally have higher approval rates, ranging from 77% to 97%, and lower denial rates, ranging from 3% to 23%, with median response times typically 0 to 1 day. Overall, the table shows that most prior authorization requests are approved, but denial rates, appeal success rates and response times vary considerably across ACA Marketplace insurers.
  1. The turnaround time for standard requests in Medicare Advantage and Medicaid managed care was shortened to 7 calendar days beginning in 2026. Timeframes for the ACA Marketplace remain the same. ↩︎
  2. CMS makes data on post-service (not pre-service/prior authorization) claims denials available for plans on the ACA FFM. ↩︎
  3. Except CVS (which had 5% market share on the ACA FFM in 2025), as the company’s prior authorization metrics for that market could not be located. ↩︎
  4. Due to the large number of smaller insurers in the ACA Marketplace, relative to Medicare Advantage and Medicaid managed care, we collected data for ACA FFM insurers that have at least 1% market share, compiled in Appendix Table 2. For consistency across market segments, only data from insurers with at least 2.5% market share were included in this analysis. ↩︎
  5. Centene includes Wellcare, Elevance includes Anthem BCBS and Wellpoint, and CVS includes Aetna. ↩︎
  6. Elevance includes Amerigroup, Independence Health Group includes AmeriHealth Caritas, and CVS includes Aetna. ↩︎
  7. Centene includes Ambetter Health; GuideWell includes Capital Health Plan (FL), BCBS of FL, Health Options (FL), and Florida Health Care Plan; Health Care Service Corp. includes BCBS plans in Montana, Oklahoma, and Texas; Elevance includes Wellpoint and Anthem BCBS. ↩︎
  8. FAQs currently on the CMS website indicate that appeals metrics should aggregate all levels of appeals, including internal and external reviews. Note that this clarification appears to have been added in early 2026. ↩︎
  9. Some insurers reported response times in days while others used hours. To standardize, we converted hours to days and report time in days. ↩︎
  10. The turnaround time for standard requests in Medicare Advantage and Medicaid managed care was shortened to 7 calendar days beginning in 2026. Timeframes for the ACA Marketplace remain the same. ↩︎

Medicare Will Spend More Than $13 Billion on the Medicare Advantage Quality Bonus Program in 2026

Published: Aug 12, 2026

Editorial Note: Originally published on July 1, 2026, this brief was updated August 12, 2026 to include additional information about the impact of the recent recalculation of star ratings by CMS on 2027 Medicare Advantage quality bonus program spending. 

The Medicare Advantage quality bonus program, established by the Affordable Care Act, increases Medicare payments to Medicare Advantage plans that qualify by having a star rating of 4 or above (on a five-star rating system). (See the KFF brief on Medicare Advantage payments for more detail.) Plans may, but are not required to, use the increase in payments to cover the cost of supplemental benefits, including reduced cost sharing, extra benefits not covered by traditional Medicare (e.g., vision, hearing and dental), lowering Part B premiums, and/or subsidizing Part D prescription drug coverage. The star ratings are intended to help consumers make informed decisions when choosing among Medicare Advantage plans and the potential for additional funding is intended to encourage plans to improve quality. However, the Medicare Payment Advisory Commission (MedPAC) and others have suggested that the star ratings incorporate too many measures, do not adequately account for social risk factors, and may not be a useful indicator of quality because star ratings are reported at the contract rather than the plan level. Medicare Advantage contracts typically include multiple plans, which may have different benefits, costs, networks, service areas, and enroll different populations (i.e., plans that are open for general enrollment and special needs plans that limit enrollment to dual-eligible individuals).

Critiques of the quality bonus program have led to calls to replace, reform or end the program. In 2018, the Congressional Budget Office estimated that eliminating the quality bonus program would lower federal spending by almost $100 billion over ten years. Given the sharp increase in both actual and projected Medicare Advantage enrollment since CBO’s analysis, the savings from eliminating the quality bonus program could be substantially higher. For example, 35 million people are enrolled in Medicare Advantage in 2026, which is 5 million more than CBO projected at the time of the analysis. The degree to which changes to the quality bonus program would impact plan quality or the availability of supplemental benefits would depend on the specifics of any proposal and how insurers modified plan offerings in response.

Recently, the Centers for Medicare & Medicaid Services (CMS) finalized changes to the star ratings system (effective for 2029 star ratings, based on the 2027 plan year performance) that include removing several administrative measures and others that CMS stated no longer meaningfully differentiate plan quality. Though this change is a step toward simplifying the quality measurement system, because it is not combined with other changes to the Medicare Advantage payment system, the change is projected to increase Medicare Advantage spending by $18.6 billion over the next 10 years. That increase in spending is in part because more Medicare Advantage plans are expected to qualify for a payment increase under the quality bonus program as a result of the changes.

This analysis examines trends in Medicare spending resulting from the quality bonus program, enrollment in plans in bonus status (plans that qualify for a benchmark increase based on their quality star rating), and how these measures vary across plan types and insurers using publicly available information on Medicare Advantage enrollment, payment rates, and quality ratings (see methods).

Key Takeaways:

  • Federal spending related to the Medicare Advantage quality bonus program will reach at least $13.4 billion in 2026, somewhat more than in 2025 ($12.7 billion), and more than four times higher than in 2015.
  • More than two-thirds of Medicare Advantage enrollees (68%) are in plans that qualify for the quality bonus program in 2026, a decline from 75% in 2025, and the lowest share since 2018.
  • The average increase in payment per enrollee because of the quality bonus program is highest for employer- and union-sponsored Medicare Advantage plans ($466) and lowest for special needs plans ($318).  
  • Medicare spending under the quality bonus program varies across firms with UnitedHealth Group receiving the largest increase in payments ($3.9 billion) because of the quality bonus program (relative to what payments would have been otherwise) and Kaiser Foundation Health Plans receiving the largest increase in payments per person ($577). The variation is largely due to the share of enrollees in plans that qualify for increases under the quality bonus program but also relates to the average star ratings of plans that qualify.

Medicare will spend more than $13 billion on the Medicare Advantage quality bonus program in 2026.

Estimated federal spending on the Medicare Advantage quality bonus program will total at least $13.4 billion in 2026, somewhat more than 2025 ($12.7 billion). Spending on the quality bonus program has increased sharply since the program started, more than quadrupling from $3.0 billion in 2015 to $13.4 billion in 2026 (Figure 1). Total spending on the quality bonus program is 2.3% of the projected payments to Medicare Advantage plans in 2026 ($574 billion).

Total Medicare Spending Under the Medicare Advantage Quality Bonus Program Will Increase to Over  Billion in 2026 (Column Chart)

These estimates are a lower bound because they assume that, on average, Medicare beneficiaries enrolled in each plan that qualifies for additional payments under the quality bonus program are of average health status as measured by their risk score (that is, having a risk score equal to 1). However, increased coding intensity in Medicare Advantage suggests the risk scores are likely higher, which would increase the additional payments. For example, MedPAC estimates the increase to risk-adjusted benchmarks under the quality bonus program will add about $16 billion in Medicare spending in 2026. The estimates also do not include additional Medicare spending that results if plans increase their bids when their benchmark is higher because of being in bonus status (See Box 1 for more detail on star ratings and Medicare Advantage payments). For example, a plan might increase its bid to increase payments to providers, add more expensive providers to its network, or retain a larger amount as profit, provided they meet medical loss ratio requirements. (The medical loss ratio is the share of premium revenues going to pay for claims versus administrative overhead and profit.)   

Medicare spending under the quality bonus program has grown faster than enrollment in Medicare Advantage, which has doubled since 2015. This spending comes at a time when the Medicare program is facing growing fiscal pressures. Medicare Advantage benchmarks (and corresponding spending) grew faster than traditional Medicare spending between 2017 and 2024 in part because of the increase in spending under the quality bonus program. The quality bonus program also exacerbates the impact of higher coding intensity and favorable selection in Medicare Advantage, which together add $76 billion to Medicare spending in 2026. (Note, the higher spending under the quality bonus program is not additive to the $76 billion.)

More than two-thirds of Medicare Advantage enrollees (68%) are in plans that qualify for the quality bonus program.

In 2026, nearly 24 million people, or 68% of Medicare Advantage enrollees, are in plans that qualify for higher payments under the quality bonus program. That compares to just under 9 million people (55%) in 2015 (Figure 2). Both the number and share of enrollees in plans that receive bonuses in 2026 declined from the previous year (26 million or 75% of Medicare Advantage enrollees) and is the lowest share since 2018. That is a result of changes to the cut points, or scores plans are required to achieve to get higher quality ratings, values that CMS recalculates every year. In particular, substantially fewer Medicare Advantage contracts achieved at least a 4-star rating in 2026 compared to the previous year (209 vs 261). Star ratings are based on a Medicare Advantage contract’s performance on about 40 different measures, such as the share of enrollees that receive certain cancer screenings and annual flu vaccinations, whether people with chronic conditions are getting recommended services, enrollees’ ratings of their health plan, and customer service. For each measure, CMS establishes “cut points”, which are used to assign a rating between one and five stars for that measure. These are then combined into an overall rating for the Medicare Advantage contract. 

More Than Two-Thirds of Medicare Advantage Enrollees (68%) are in Plans That Qualify for Bonuses in 2026, a Somewhat Smaller Share Than in 2025 (Stacked column chart)

The average annual increase in payments per person under the quality bonus program are highest for employer- and union-sponsored plans.

Employer- and union- sponsored Medicare Advantage plans account for a larger share of spending under the quality bonus program (20%, or $2.6 billion) than enrollment in Medicare Advantage (16%) (Appendix Table 1). Consistent with this, and similar to previous years, the average increase in payments per person as a result of the quality bonus program to group employer- and union-sponsored plans ($466) are higher than for individual ($381) or special needs plans ($318) (Figure 3).     

Annual Increase in Payments Per Person Under the Medicare Advantage Quality Bonus Program are Highest for Employer Plans (Line chart)

The increase in payments per enrollee stemming from the quality bonus program are higher for employer- and union-sponsored plans because these plans have higher average star ratings, resulting in a larger share of enrollees receiving coverage from plans that qualify for bonuses. Across the entire period of 2015 to 2026, the share of all enrollees in employer- or union-sponsored plans that qualified for the quality bonus program never dropped below 80%. In contrast, the share of enrollees in individual and special needs plans that qualified for the quality bonus program exceeded 80% in only one year – 2023 (Figure 4).

The Share of Enrollees in Medicare Advantage Plans Sponsored by Employers That Qualified for the Quality Bonus Program has Exceeded 80% Since 2015 (Line chart)

Special needs plans serve higher need beneficiaries, including people who are dually eligible for Medicare and Medicaid and people who require an institutional level of care. Despite critiques of the quality star rating system, lower star ratings for special needs plans, on average, raise questions about how well these plans are serving the needs of their enrollees. The higher share of employer- and union-sponsored plans that qualify for the quality bonus program also raises questions about whether these plans, which are restricted to retirees of specific employers or unions, include more generous coverage or extra benefits. However, gaps in Medicare Advantage data, including the lack of information about the costs and benefits of employer- and union-sponsored plans, mean it is difficult to examine these questions.

Total Medicare spending under the quality bonus program varies across Medicare Advantage parent organizations.

UnitedHealth Group enrolls just over one-quarter (26%) of Medicare Advantage enrollees and is expected to receive 29% of total Medicare spending under the quality bonus program, or $3.9 billion dollars in 2026 (Figure 5). Humana Inc., which has the second largest share of Medicare Advantage enrollment (20%), will receive a disproportionately smaller share of bonus spending (11%), or $1.5 billion in 2026. Humana’s average star rating dropped considerably for the 2025 plan year (which is the year used for 2026 bonus eligibility), after the star rating for one of its largest contracts dropped from 4.5 to 3.5. Humana sued CMS over the change, but to date, the courts have sided with the Administration.

The average increase in payments per enrollee under the quality bonus program ranges from $23 for people in Centene Corporation plans to $577 for those in plans sponsored by Kaiser Foundation Health Plans. The variation in total bonus spending across firms corresponds to differences in the share of enrollees in plans that are eligible for the quality bonus program, which is based on the ratings of those plans. Virtually all of the more than 2 million enrollees in a plans sponsored by Kaiser Foundation Health Plans (100%) are in a plan that receives increased payments under the quality bonus program because it has a quality rating of at least four stars, while just 6% of Centene’s 938,000 Medicare Advantage enrollees are in a plan that receives bonus payments in 2026. The only Centene sponsored Medicare Advantage contracts that qualify for the quality bonus program payments in 2026 are those that are too new or have too low enrollment to receive star ratings. Differences also reflect variation in the star ratings of plans that qualify for the quality bonus program, because plans with at least 4.5 stars get a larger increase.

Total Medicare Spending Under the Quality Bonus Program Varies Across Medicare Advantage Parent Organizations (Table)

The recent recalculation of star ratings by CMS will increase spending under the quality bonus program in 2027.

In recent years, Medicare Advantage insurers have increasingly challenged the star ratings calculations, and have prevailed in a handful of cases, prompting CMS to recalculate the ratings on occasion. Most recently, in response to a decision following a legal challenge from Clover Health, CMS recalculated the 2026 star ratings for all plans (which will affect the 2027 payment year). CMS has only revised the star ratings for plans that saw an increase as a result of the recalculation.

Higher star ratings have three potential effects: 1) New eligibility for benchmark increases under the quality bonus program when the recalculated rating is at least 4 stars and the previous rating was less than 4 stars; 2) increased rebate percentage if recalculated star rating is associated with a higher rebate category (the rebate percentage is 70% of the difference between the benchmark and bid when the rating is at least 4.5 stars, 65% when the rating is 3.5 to 4.5 stars, and 50% when the rating is less than 3.5 stars); and 3) new 5-star special enrollment period (SEP) when the recalculated star rating is 5 stars and previous star rating was less than 5 stars.

KFF estimates that federal Medicare Advantage payments to insurers under the quality bonus program will be about $600 million higher in 2027 than they would have been if CMS had not recalculated the star ratings, with additional impacts for plans that receive higher rebate percentages but do not qualify for the quality bonus program. UnitedHealth Group will see the largest increase, followed by Clover Health, Blue Cross Blue Shield of Alabama, Humana, and CVS Health Corporation. Higher payments to Medicare Advantage insurers as a result of benchmark and rebate increases could translate into more generous benefits, lower cost sharing, or higher plan margins, while the additional SEP gives impacted plans an opportunity to attract new enrollees mid-year. CMS has appealed the decision, however, so there is uncertainty as to whether changes in methodology and their impact on payments will continue beyond the 2027 plan year.

Box 1. Medicare Advantage Star Ratings

A key feature of the quality bonus program is the star rating system. Star ratings are used to determine two parts of a Medicare Advantage plan’s payment: (1) whether the plan is eligible for a bonus, and (2) the portion of the difference between the benchmark and the plan’s bid that is paid to the plan. The benchmark is the maximum amount the federal government will pay for a Medicare Advantage enrollee and is a percentage of estimated spending in traditional Medicare in the same county, ranging from 95 percent in high-cost counties to 115 percent in low-cost counties. The bid is the plan’s estimated cost for providing services covered under Medicare Parts A and B.

Since 2015, plans that receive at least four (out of five) stars have their benchmark increased. For most plans in bonus status, the benchmark is increased by five percentage points. Plans in “double bonus” counties – defined as urban counties with low traditional Medicare spending and historically high Medicare Advantage enrollment—have their benchmark increased by 10 percentage points. In addition, the benchmarks for plans without ratings due to low enrollment or being too new are increased by 3.5 percentage points. The benchmarks are capped and cannot be higher than they would have been prior to the ACA. This can result in plans that are eligible under the quality bonus program receiving a smaller increase to their benchmark, or in some cases, no increase at all.

The benchmark increases under the quality bonus program for qualifying plans mean that per enrollee payments are higher than if the plan did not qualify. There is no separate bonus payment. Rather, the bid and/or rebate components of the payment are higher.

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

Appendix
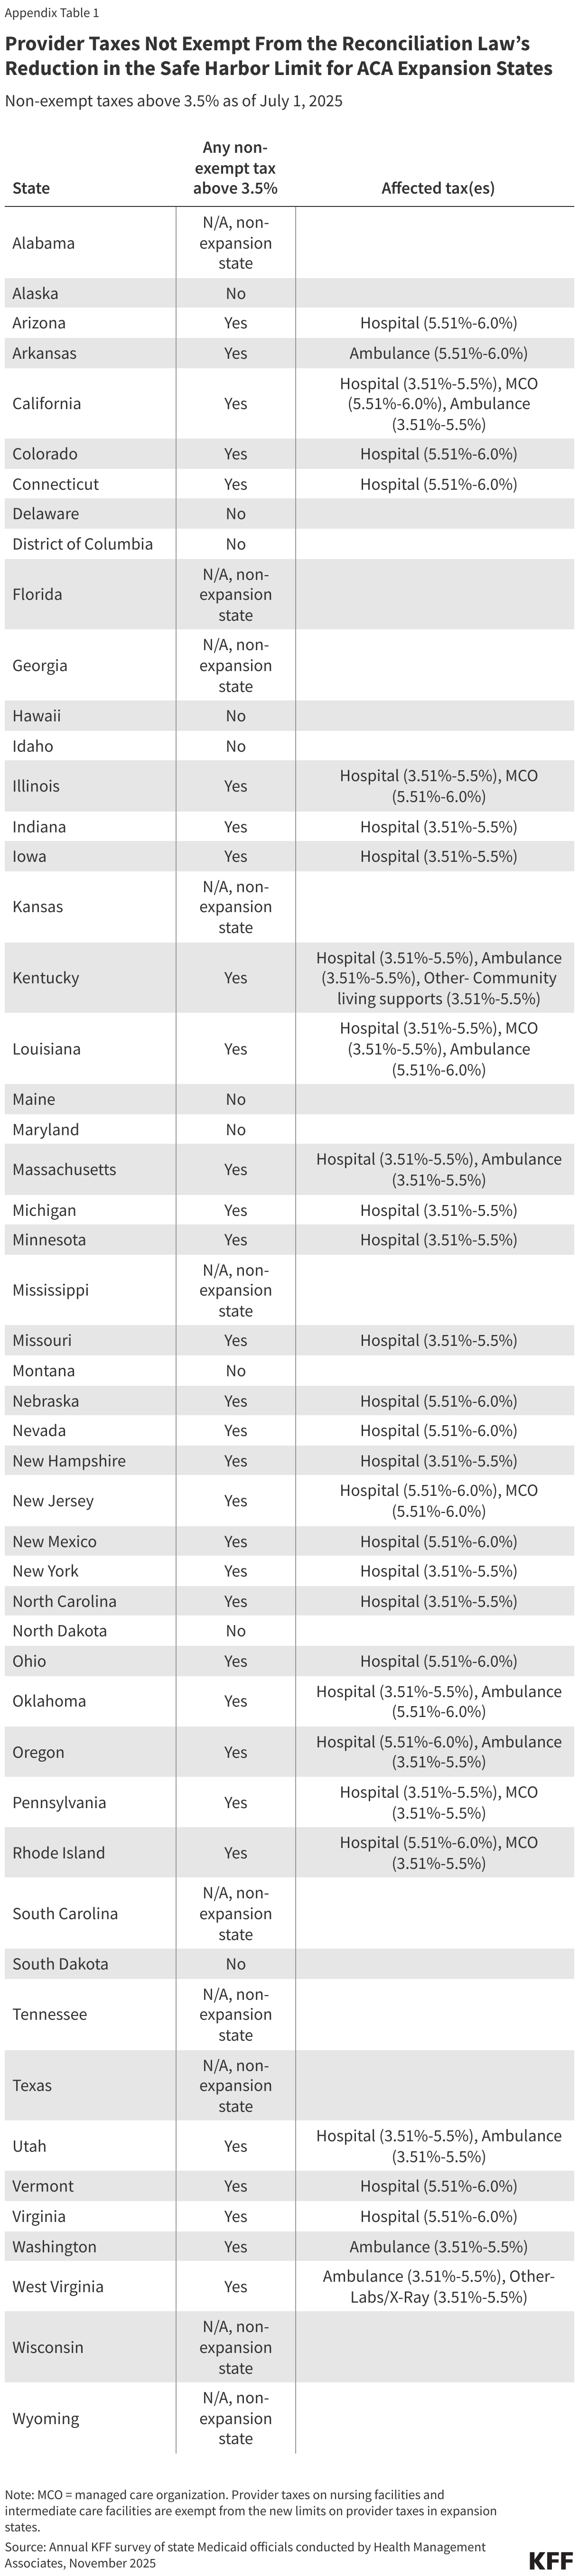
Total Medicare Spending Under the Quality Bonus Program by Type of Medicare Advantage Plan, 2015 - 2026 (Table)
Average Annual Increase in Payment Per Enrollee Under the Quality Bonus Program by Medicare Advantage Plan Type, 2015 - 2026 (Table)

Methods

This analysis uses data from the Centers for Medicare & Medicaid Services (CMS) Medicare Advantage Enrollment, Crosswalk and Landscape files for the respective year.This analysis includes HMO, POS, local PPO, regional PPO, and PFFS plans. Enrollment counts in publications by firms operating in the Medicare Advantage market, such as company financial statements, might differ from KFF estimates due to inclusion or exclusion of certain plan types, such as SNPs or employer plans.To calculate federal spending on the quality bonus program, we first obtained information on star ratings from the Part C and Part D Performance Data, Star Ratings Data Table for the previous plan year. These are the ratings on which a plan’s benchmark is based. We then determined each plan’s benchmark using these data and information from the Medicare Advantage Rate Book, Rate Calculation Data, which provides the benchmark by county for plans with a 5%, 3.5% and 0% bonus. A plan’s increase in payment per enrollee under the quality bonus program is equal to the difference between its quality adjusted benchmark (either the 5% or 3.5% bonus rate) and the benchmark if the plan was not in bonus (0% bonus rate), multiplied by the relevant percentage based on its star rating and year (for example, 65% for plans with 4 stars and 70% for plans with at least 4.5 stars in 2026). The increase per enrollee is multiplied by enrollees in March of each year to get total spending. Actual bonus spending will depend on the risk scores of Medicare Advantage enrollees. According to the plan payment data release by CMS, the average risk score of MA enrollees was above 1 for every year from 2015 through 2024 (the most recent year for which data are available), meaning our estimates likely understate actual spending.

The White House Takes Another Shot at Changing U.S. Childhood Vaccine Recommendations

Published: Aug 11, 2026

A new Executive Order (EO) released by the White House on Monday is the latest in a series of administration actions seeking to change U.S. childhood vaccine recommendations. It follows:

The new EO reiterates several previously issued recommendations, including that U.S. childhood vaccines should be “aligned with scientific evidence and best practices from peer, developed countries” and that childhood immunizations should fall into the three categories outlined above. As with the January 5 memo, the EO reduces the number of diseases targeted by routine childhood vaccination from 17 to 11 and the number of routine vaccines from 13 to 7. But it also contains new directives, including calling on the HHS Secretary to offer some childhood vaccines such as measles, mumps, and rubella (MMR) as “single vaccines rather than combination products”; aligning vaccine recommendations with findings to be released by a federal panel known as the “HHS Task Force on Safer Childhood Vaccines”; and directing the Attorney General to advance legal actions challenging state laws that conflict with “parental authority, religious freedom, disability accommodations, and equal protection under the law.” 

The administration has indicated these actions are intended to align the U.S. with peer countries, particularly Denmark. Prior KFF analysis has found, however, that Denmark itself is an outlier among “peer” nations, recommending vaccines against 10 diseases while most European countries recommend vaccines for 15 or more. Moreover, the EO’s directive to split the MMR vaccine into separate shots (a policy that could not be put into practice yet as no single component vaccine is currently licensed in the U.S.) would actually cause the U.S. to diverge from the policies of peer, developed nations, including Denmark. No European country, Canada, or Australia recommend separate vaccines over combination MMR vaccines (Japan currently recommends a combination measles rubella vaccine and this year began producing MMR for domestic use for the first time in 30 years).

President Trump said in a Monday press conference that the MMR shot can be “quite lethal” and that splitting up and giving the shots over multiple appointments is safer, although there is no evidence to support this claim. When countries have moved away from combination MMR vaccinations in the past, such as Japan beginning in the 1990s, measles, mumps, rubella outbreaks increased – a sobering prospect given the U.S. is already facing a historically high and growing number of measles cases this year.

The EO empowers a HHS Task Force – comprised of federal officials rather than external experts – to assess “timing and sequencing of all core childhood vaccines” and adjust the federal vaccine schedule. This could, in effect, bypass the CDC and its external Advisory Committee on Immunization Practices (ACIP), the traditional vehicles for federal vaccine recommendations, perhaps an attempt to implement administration vaccine priorities that have so far stymied by federal courts. Even so, it is not clear how many U.S. states, which have primary responsibilities in determining which childhood vaccines are required for school entry and other key vaccine policies, would adopt recommendations from this relatively unknown Task Force. In fact, most states – 30 including DC – have already made moves to decouple their vaccine policies from federal government recommendations for one or more childhood vaccines, instead relying on prior recommendations, state recommendations, and/or those of external entities such as American Academy of Pediatrics (AAP). Any recommendations from the Task Force are also unlikely to change how insurance covers childhood vaccinations given that private insurers have pledged to maintain existing childhood vaccine coverage through the end of 2027, and coverage through federal programs such as Vaccines for Children are not expected to change even with the recategorization of childhood vaccines contained in the order, a point confirmed by the White House itself on Monday.

Given ongoing legal challenges to the administration’s vaccine actions and declining influence of federal recommendations on states vaccine policy decisions, it is not clear how much the new EO can shift U.S. vaccine policy. Still, it could sow further confusion among parents already distrustful of federal guidance, and serve to exacerbate the existing partisan divide in the country on vaccine policy, and prove to be unpopular. A KFF poll from January this year, after HHS announced its earlier changes to the federal childhood vaccine schedule, found that adults who had heard about those changes were twice as likely to say it would have a negative impact on children’s health than a positive one. Ultimately, the effect of implementing these changes could be to raise the risk for further outbreaks of childhood diseases such as measles.

Variability in Reimbursement Rates for State-funded Abortion Services for Medicaid Enrollees: A 2026 Update

Authors: Brittni Frederiksen, Olivia Podber, and Alina Salganicoff
Published: Aug 7, 2026
  • Among states that use state-appropriated funds to pay for abortion for Medicaid enrollees, variability in abortion payment rates for the same procedures is considerable. Twenty-one states currently use their own funds to cover abortion services for Medicaid enrollees beyond the limits imposed by the federal Hyde Amendment, which bans federal funding of abortions in cases other than pregnancies that result from rape, incest, or are a life threat. In these states, Medicaid medication abortion rates range from $162 (RI) to $869 (WA) (median $597); dilation and curettage (D&C) procedure rates go from $126 (RI) to a high of $1,000 (NY) (median $378); and dilation and evacuation (D&E) procedure rates vary from $126 (RI) to $1,920 (IL) (median $636).  
  • Only a few states significantly increased their state-funded reimbursement rates for abortion services for Medicaid enrollees in the past two years. Most states that cover abortions for their enrollees have not changed or only modestly increased their reimbursement rates. Among the states that increased D&C rates, only 5 did so at or above the rate of health care inflation. Similarly, among states that increased D&E reimbursement rates, only 6 increased rates at or above the rate of health care inflation over the past two years. Over half (57%, 12 states) have not increased D&C procedure reimbursement rates, and 52% (11 states) have not increased D&E procedure reimbursement rates. 
  • Despite the increased complexity of abortion procedures later in pregnancy, Medicaid reimbursement rates are not substantially higher than rates for earlier-stage procedures in most states. Reimbursement rates for abortions later in pregnancy typically do not reflect the increased complexity and costs associated with later-stage care. The median reimbursement rate for states that fund abortions for Medicaid enrollees was $378 for D&C—typically used earlier in pregnancy—vs. $636 for D&E, which is generally used for abortion procedures performed later in pregnancy. These rates are considerably lower than previously published research on self-pay abortion charges for the same procedures.

Since the Dobbs decision in 2022 overturning Roe v. Wade, 13 states have banned the provision of abortion with few exceptions. In the remaining states where abortion is legal, another barrier to abortion services has been the federal Hyde Amendment, which prohibits the use of federal Medicaid funds for abortion with limited exceptions for pregnancies that endanger the life of the pregnant person, or that result from rape or incest. States may use their own revenues to pay for abortion services for Medicaid enrollees beyond the federal financing restrictions, and 21 currently use their own state funds to pay for abortions for Medicaid enrollees, while 16 states & DC where abortion provision is not banned follow the Hyde Amendment restrictions (Figure 1). Medicaid reimbursement rates are established by the states under broad federal guidelines and have historically been lower than those paid by Medicare and are even lower relative to private insurance rates.

In the case of Medicaid, lower reimbursement rates can lead to abortion providers experiencing financial shortfalls, challenging their long-term sustainability and ability to serve Medicaid enrollees. Lower reimbursement rates have been linked to higher out-of-pocket costs for Medicaid beneficiaries, who are overwhelming low-income, further constraining their access to abortion care. 

To understand the status of Medicaid payment for abortion services four years post-Dobbs, KFF researchers reviewed Medicaid physician fee schedules for medication and procedural abortions in states that do not ban abortion, updating an analysis first published in 2024. This analysis focuses on states where abortion provision is not banned, including those using state funds to pay for abortions for Medicaid enrollees as well those that only cover abortions under Hyde exceptions, and it excludes the 13 states where abortion provision is banned. 

Figure 1 is a map of the United States titled, “21 States Provide Funds to Pay for Abortion Services for Medicaid Enrollees.” States are color-coded into three categories: blue indicates states that use their own funds to pay for abortions under Medicaid (21 states), orange indicates states that follow the federal Hyde Amendment restrictions (16 states and Washington, DC), and red indicates states where abortion is banned (13 states). States that use their own state funds to pay for abortions under Medicaid (blue states) are concentrated on the West Coast, the Northeast, and parts of the Midwest and Southwest. States where abortion is banned (red states) are concentrated across the South and parts of the Great Plains. States that follow the federal Hyde Amendment restrictions, but do not ban abortion (orange states) are primarily located in the Mountain West, Midwest, and Southeast. The map includes data current as of July 16, 2026.

How Abortion Payment Rates Are Structured

Medicaid services are financed via two pathways: fee-for-service (FFS) and managed care arrangements. The reimbursement rates presented in this brief are for FFS claims, as contracted managed care rates are not typically publicly available. The FFS reimbursement rates reported in this brief are for non-facility (e.g., outpatient clinics or physician offices), provider-only rates (e.g., excluding any facility rates), since most abortions are performed outside of a hospital setting. States such as Connecticut, Massachusetts, Nevada, and Washington use different reimbursement fee schedules for family planning and abortion clinics. These reimbursement rates are often higher than physician fee schedules. This analysis uses the family planning and abortion clinic rates, when available.

State Medicaid programs also differ in the payment structures they use for abortion services. Some states use a bundled reimbursement structure for abortion services, where ancillary services provided alongside the abortion are included in the bundled payment rate. Other states use unbundled billing, and providers can bill separately for all services provided with the abortion. Additional services often billed for on the day of the abortion in states that use unbundled codes may include an ultrasound, administered medication, a nerve block, and Rh testing, which are outlined in coding guides developed by the Reproductive Health Access Project for manual vacuum aspiration abortion and medication abortion. Median reimbursement rates for each of these services from state Medicaid physician fee schedules are reported in the tables throughout this brief.

Even when Medicaid reimburses for abortion services, providers have reported that Medicaid reimbursement rates are substantially lower than what they receive from self-pay patients. Because there are limited and outdated data on the actual cost of providing abortion care, self-pay prices can serve as a useful proxy for provider costs, although they may underestimate true costs if they reflect discounts provided to patients by abortion funds. Research conducted before the Dobbs decision illustrates the breadth of this reimbursement gap. A 2020 study reviewed 2017 Medicaid and Medicare physician fees schedules for D&C and D&E procedures across 45 states and D.C. and found that median Medicaid reimbursement rates for first- and second-trimester abortions covered only 37% and 41% of the amount charged to self-pay patients for the procedures, respectively. The study did not address reimbursement rates for abortions after the second trimester. Providers also reported instances in which they received no reimbursement for abortions that were eligible for Medicaid coverage under the Hyde Amendment. The study's authors concluded that this reimbursement gap, particularly when combined with inconsistent reimbursement practices, may further discourage providers from participating in Medicaid.

More recent data on self-pay prices support these findings. A 2024 report on self-pay charges for abortion services from 2017 to 2023 found median charges of $563 for medication abortion, $650 for a first-trimester procedural abortion (D&C), and $1,000 for a second-trimester abortion (D&E). These quoted self-pay prices are substantially higher than Medicaid reimbursement rates in many states, reinforcing that a gap exists between what providers typically charge and what Medicaid pays. 

In 2023, medication abortion, a two-drug regimen using mifepristone and misoprostol that is FDA-approved to terminate pregnancies up to 10 weeks in the U.S., accounted for 65% of all abortions. This share has increased since the FDA removed the in-person dispensing requirements in 2021, making medication abortion via telehealth, mail, and pharmacies more accessible. 

Medication abortion can be billed using three separate procedure codes, and often all three codes are billed at the same time. There are codes for two pharmaceuticals—mifepristone (HCPCS S0190) and misoprostol (HCPCS S0191)—as well as a global medication abortion code (HCPCS S0199) that includes all affiliated services and supplies (e.g., patient counseling, office visits, confirmation of pregnancy by HCG, ultrasound to confirm duration of pregnancy, ultrasound to confirm completion of abortion). 

States typically take two approaches to reimburse for medication abortion services: (1) a bundled payment using the global medication abortion code plus the medications (billed either through medical services or pharmacy billing channels); or (2) payment for separate services, like office visits and ultrasounds, plus the medications. 

Twenty out of 21 states that use state funds to pay for abortion services for Medicaid enrollees list reimbursement rates for at least one of the three medication abortion codes, with 16 listing rates for the global medication abortion code, 13 listing rates for mifepristone, and 12 listing rates for misoprostol. The one state not accounted for is New York; while they do not reimburse for the global medication code, on their publicly available fee schedule they reimburse at the “cost” of the drugs to abortion providers for both mifepristone and misoprostol. The median Medicaid reimbursement rate for the global medication abortion code is $514, ranging from a low of $81 in Rhode Island to a high of $825 in Washington (Figure 2). The median reimbursement rate for mifepristone is $81, ranging from a low of $43 in Washington to a high of $128 in New Jersey. The median reimbursement rate for misoprostol is $2, which ranges from less than $1 in Washington to $22 in Illinois. When the median amounts for all three medication abortion codes are summed together, the median reimbursement rate for medication abortion is $597. However, the range of summed codes across states is quite large, from $162 in Rhode Island to $869 in Washington.

Figure 2 is a horizontal bar chart titled, “Fee-For-Service Reimbursement Rates for Medication Abortion in States That Cover Abortion Services for Medicaid Enrollees.” The chart shows Medicaid reimbursement rates for three procedure codes: S0190 (mifepristone), S0191 (misoprostol), and S0199 (global medication abortion) for 16 of  the 21 states that use state funds to cover abortion services for Medicaid enrollees and list reimbursement for the global medication abortion code. Each state's total reimbursement is shown as a stacked horizontal bar with dollar amounts labeled.

At the top, the 2026 median reimbursement totals 7, consisting of  for mifepristone and 4 for the global medication abortion code. The 2026 mean reimbursement totals 4, consisting of  for mifepristone and 1 for the global code.

Among the states shown, Washington has the highest total reimbursement at 9 and Rhode Island has the lowest at (2).

Most of the reimbursement in each state comes from the global medication abortion code, while reimbursement for mifepristone is generally much smaller, and misoprostol reimbursement is minimal or not separately shown in most states.

For the five states that do not use the bundled, global code for medication abortion, the sum of the rates for mifepristone and misoprostol alone range from $44 in Minnesota1 to $131 in New Jersey. In these states, providers may bill separately for ancillary services, which could potentially add additional reimbursement (Table 1).

Table 1 titled, "Median Fee-For-Service Reimbursement Rates for Services Typically Billed with Unbundled Medication Abortion in States That Cover Abortion Services for Medicaid Enrollees." The table includes states that use unbundled reimbursement for medication abortion, including Alaska, Minnesota, Montana, New Jersey, and New York. The table lists medication abortion services billed alongside mifepristone and misoprostol, including transvaginal ultrasounds, limited ultrasounds, transabdominal ultrasounds, Micro Rhogam, and/or office visits. The table lists the specific billing codes, median reimbursement rates, and the number of state fee schedules used to calculate each median.

The medication abortion reimbursement rates reported in this brief apply to services provided in outpatient clinics or physicians’ offices and do not specifically address reimbursement rates for telehealth medication abortion for either bricks-and-mortar or online-only providers. Telehealth has become an increasingly common mode of medication abortion provision; in 2025, approximately 28% of all abortions were medication abortions provided through telehealth, representing a 27% overall increase from 2024. Although research on Medicaid reimbursement rates for telehealth medication abortion is limited, a 2024 report from the National Health Law Program found that, across six states (Illinois, Minnesota, New Mexico, New York, Rhode Island, and Washington), there was overall payment parity for synchronous video telehealth service delivery under Medicaid compared to in-person medication abortion service delivery. However, many of these states adopted temporary telehealth payment parity policies in response to the COVID-19 public health emergency, and some of those policies have not yet been made permanent, limiting the generalizability of these findings. 

While most states that use their own funds to pay for abortion services for Medicaid enrollees list reimbursement rates for medication abortion, only half of the states that follow Hyde restrictions list reimbursement rates for medication abortion, and median reimbursement in these states is substantially lower (see Appendix Table 1). Beyond the issue of failing to publish reimbursement rates for medication abortion, a 2025 U.S. Government Accountability Office (GAO) report found that 14 states participating in the Medicaid Drug Rebate Program (MDRP) were not complying with federal requirements to cover FDA-approved medication abortion drugs, even in circumstances permitted under the Hyde Amendment, such as rape, incest, or life-endangerment. The GAO reported these instances of noncompliance to the Centers for Medicare and Medicaid Services (CMS) in late 2025. 

Dilation and curettage (D&C) is a common abortion procedure that can be used up to approximately 16 weeks of pregnancy. Medicaid physician fee schedules for fee-for-service reimbursement rates were published online for D&C procedures in all 21 states that use state funds to reimburse for abortion services for Medicaid enrollees beyond Hyde exceptions (Figure 3). The median reimbursement rate for a D&C procedure in these states was $378, ranging widely from $126 in Rhode Island to $1,000 in New York. Since 2024, Pennsylvania2 and Colorado have shifted from following Hyde restrictions to using state funds to pay for abortion for Medicaid enrollees. In the past two years, Pennsylvania increased their rate for D&C procedures by 833%, Colorado increased their reimbursement rate by 378%, and Maryland increased their rate by 154%. Beyond these outliers, most states have not increased their rates or increased them only slightly. Nine of 21 states that use state funds to cover abortion for Medicaid enrollees increased rates, but of those, only 5 states increased rates at or above the health care inflation rate over the past two years. Of the remaining 12 states that did not increase rates, 6 states have not changed their D&C reimbursement rates, and 6 states have decreased their rates between 2024 and 2026. In states that only reimburse for abortions in cases of pregnancies resulting from rape, incest, and life endangerment, payment rates were considerably lower (see Appendix Table 2).

Figure 3 is a table titled, "Fee-For-Service Reimbursement Rates for D&C Procedures in States That Fund Abortion Services for Medicaid Enrollees." The table lists, by state, Medicaid reimbursement rates for dilation and curettage (D&C) abortion procedures in 2024 and 2026 and includes a line graph depicting the change in rates over the two time periods. It also includes a percentage change column that ranges from -10% in New Jersey (7 to 8) to 833% in Pennsylvania ( to 5) that recently started using state funds to pay for abortion services for Medicaid enrollees.

Other services may be billed and reimbursed on the day of a procedural abortion including ultrasound, anesthetic medication administration like lidocaine and methergine, or a nerve block for pain. In some states, the reimbursement rates for these additional services are not publicly posted (Table 2). Illinois and New Mexico reimburse procedural abortions (CPT codes 59840 and 59841) as bundled codes and will not pay for other related services when these codes are billed. Therefore, Illinois and New Mexico were removed from the calculations in the table below detailing median ancillary rates for services that may be provided at the time of the abortion. 

Table 2 is titled, "Median Fee-For-Service Reimbursement Rates for Services Typically Billed with a D&C Procedure in States That Cover Abortion Services for Medicaid Enrollees." The table lists dilation and curettage abortion services billed alongside D&C procedures, including insertion of cervical dilator, transvaginal ultrasound, limited ultrasound, lidocaine, methergine, nerve block injection, surgical tray, specimen handling, and Micro Rhogam. The table lists the billing codes associated with those services, median reimbursement rates, and the number of state fee schedules included to calculate each median.

For a dilation and evacuation (D&E) procedure, which is often used in the second trimester, the reimbursement rates similarly varied widely by state (Figure 4). In states that fund abortion services for Medicaid enrollees, the median reimbursement rate for a D&E procedure was $636, ranging from a low of $126 in Rhode Island to a high of $1,920 in Illinois. Since 2024, Colorado increased their D&E reimbursement rate by 492%, Pennsylvania increased their rate by 227%, and Massachusetts by 99%. Beyond those substantial reimbursement rate increases, 10 of 21 states that use state funds to pay for abortion for Medicaid enrollees increased D&E reimbursement rates for Medicaid providers between 2024 and 2026, but only 6 increased their rates at or above the rate of health care inflation. Of the remaining 11 states that did not increase rates, 7 have not changed their D&E reimbursement rates, and 4 have decreased their rates over the past two years. As with D&C procedures, the median reimbursement rate for D&E procedures in states that pay for abortions for Medicaid enrollees is higher than in states that limit abortion coverage to those cases permissible under the Hyde Amendment (see Appendix Table 3).

Figure 4 is a table titled, "Fee-For-Service Reimbursement Rates for D&E Procedures in States That Fund Abortion Services for Medicaid Enrollees." The table lists, by state, Medicaid reimbursement rates for dilation and evacuation (D&E) abortion procedures in 2024 and 2024 and includes a line graph depicting the rate of change over the two time periods.  It also includes a percentage change column that ranges from -8% in New Jersey (4 to 6) to 492% in Colorado (5 to 68), which recently started using state funds to pay for abortion services for Medicaid enrollees.

As with D&C procedures, providers will often bill for other services provided with the D&E procedure if the code is not a bundled code (Table 3). In line with D&C procedures, Illinois and New Mexico use bundled rates for D&E procedures that include ancillary services and, therefore, are not included in the calculations in the table below.  

Table 3 is titled, "Median Fee-For-Service Reimbursement Rates for Services Typically Billed with a D&E Procedure in States That Cover Abortion Services for Medicaid Enrollees." The table lists common dilation and evacuation abortion services billed alongside D&E procedures, including insertion of cervical dilator, transvaginal ultrasound, limited ultrasound, lidocaine, methergine, nerve block injection, surgical tray, specimen handling, and Micro Rhogam. The table lists the billing codes associated with those services, median reimbursement rates, and the number of state fee schedules included to calculate each median.

Abortion Financing, Cost, and Medicaid Policy Considerations

Given that D&E procedures are typically provided later in pregnancy and are more costly and complex procedures, it would follow that reimbursement would be substantially higher than for D&C procedures, which are typically done earlier in pregnancy. The majority of states (27 of 38) without bans—including Hyde and non-Hyde states—reported a Medicaid reimbursement rate difference that was less than $200 (Figure 5). Three states (Rhode Island, Nebraska, & Wisconsin) reimburse for first and second trimester abortions at the exact same rate, failing to account for the differences in cost and complexity of these different procedures, leaving providers to either be exposed to financial losses if they provide abortions later in pregnancy or decline to accept Medicaid patients.

Figure 5 is a horizontal bar chart titled, “Difference Between Reimbursement Rates for D&C and D&E Procedures, 2026.” The chart compares Medicaid reimbursement rate differences in first and second trimester abortions per state, split up by Non-Hyde and Hyde states. Non-Hyde states range from reimbursement rate differences from alt=

In analyzing the role of Medicaid in abortion financing, the Guttmacher Institute’s 2021-2022 Abortion Patient Survey found 62% of abortion patients living in states that funded abortion beyond Hyde restrictions used Medicaid to pay for their abortion. Comparatively, for abortion patients living in Hyde restricted states, 82% paid out of pocket for their care, with two-thirds of those surveyed reporting they had to raise money to afford their abortion, often through accruing debt, relying on financial subsidies from abortion funds or clinic discounts, or asking friends and family. Abortion funds have long been relied on as a safety-net option for those in need of assistance in paying for their abortion, but a post-Dobbs trend of increased requests for support coupled with decreased donations leaves funds in precarious and depleted financial positions.  

These disparities in how abortion care is financed highlight the fact that insurance coverage alone is insufficient to assure access, particularly when providers’ reimbursement policies inadequately support the costs of the full range of abortion services. While reimbursement for care after the second trimester is not directly addressed in this report, a recent study investigated self-pay prices paid by patients seeking later abortion care and found that prices increased with gestational stage, while, inversely, provider and clinic availability and Medicaid coverage declined. Low Medicaid reimbursement for these services may further exacerbate reproductive access inequities for Medicaid enrollees.  

Beyond implications on patient affordability, reimbursement rates also affect providers’ ability to provide abortions to all patients regardless of payor. As with all health services, the cost of providing abortions has grown in all states as the costs of medical equipment and personnel increase annually. In addition, abortion providers face expenses that are not incurred by most other outpatient clinics such as security costs to keep their staff and patients safe from anti-abortion activities, such as extra security guards, cameras, staff background checks, and bulletproof windows. Increased safety concerns and costs have also made it difficult to retain the abortion clinic workforce.  

Appendix table 1 is titled, "Medicaid Fee-For-Service Physician Fee Schedule Reimbursement Rates for Medication Abortion, 2026." The table lists, by state (split into Non-Hyde and Hyde States) reimbursement rates for S0190 (mifepristone), S0191 (misoprostol), and S0199 (global medication abortion), and a link to each state's Medicaid physician fee schedule.
Appendix table 2 is titled, "Medicaid Fee-For-Service Physician Fee Schedule Reimbursement Rates for D&C Procedures, 2017 to 2026." The table lists, by state (split into Non-Hyde and Hyde States) reimbursement rates for D&C (CPT code 59840) in 2017, 2024, and 2026, includes the percent change from 2017 to 2024, 2017 to 2026, and 2024 to 2026, and a link to each state's Medicaid physician fee schedule.
Appendix table 3 is titled, "Medicaid Fee-For-Service Physician Fee Schedule Reimbursement Rates for D&E Procedures, 2017 to 2026." The table lists, by state (split into Non-Hyde and Hyde States) reimbursement rates for D&E (CPT code 59841) in 2017, 2024, and 2026, includes the percent change from 2017 to 2024, 2017 to 2026, and 2024 to 2026, and a link to each state's Medicaid physician fee schedule.
A prior version of this brief was originally posted March 2024. If interested in a copy of the prior brief, please to write to womenshealth@kff.org.

  1. MN reimbursement reflects data from the publicly available fee schedule, but the state legislature increased abortion payments by 20% as of January 2024. These updated rates are not reflected in this reporting.  ↩︎
  2. Under the recent Commonwealth Court ruling, Pennsylvania Medicaid is legally required to cover abortion care as of July 15, 2026. However, the Pennsylvania Department of Human Services (DHS) is still in the process of establishing the necessary billing and reimbursement system to process coverage. ↩︎