Tracking Implementation of the 2025 Reconciliation Law Medicaid Work Requirements

Updated on:

KFF Resources on Medicaid Work Requirements

Work requirements overview:

Medical frailty exemption:

Implementation of work requirements:

50-state survey of Medicaid eligibility and enrollment policies:

Research and analysis on Medicaid and work:

1115 work requirement waivers:

Work requirements implications and state experience:

Arkansas work requirement experience:

KFF Polling on Work Requirements:

Beyond the Data by KFF CEO Drew Altman:

Medicaid/CHIP Monthly Enrollment Tracker

Published: Sep 8, 2026

Note: The data presented below are updated monthly as new Medicaid/CHIP enrollment data become available.

This tracker presents the most recent data on monthly Medicaid and Children’s Health Insurance Program (CHIP) enrollment reported by the Centers for Medicare & Medicaid Services (CMS) as part of the Performance Indicator Project. It includes data for Medicaid and CHIP and reports enrollment data for children and adults. The data are generally the most recent data available and are useful for reporting trends in Medicaid enrollment. However, the data only capture full-benefit enrollees, excluding those who receive limited benefits, such as those who receive family planning services only, and consequently, do not provide a full count of the total population enrolled in Medicaid. Additionally, these data cannot be used to monitor changes in enrollment by eligibility pathway, including for adults in the Medicaid expansion group.

The 2025 reconciliation law included significant changes to Medicaid, including requiring adults in the expansion group and in certain 1115 waiver programs to meet new work and reporting requirements starting January 2027. These changes are expected to reduce Medicaid enrollment over the next 10 years relative to what would have been expected under current law. Enrollment data for the full Medicaid population is available here, and for more information on how implementation of Medicaid work requirements is affecting Medicaid expansion enrollment, please see Tracking Implementation of the 2025 Reconciliation Law Medicaid Work Requirements.

The figures below show Medicaid and CHIP enrollment from February 2020 through the most current month of available data. Figures include enrollment for adults and children in Medicaid/CHIP and for Medicaid only and CHIP only. Key enrollment data and trends as of May 2026 include:

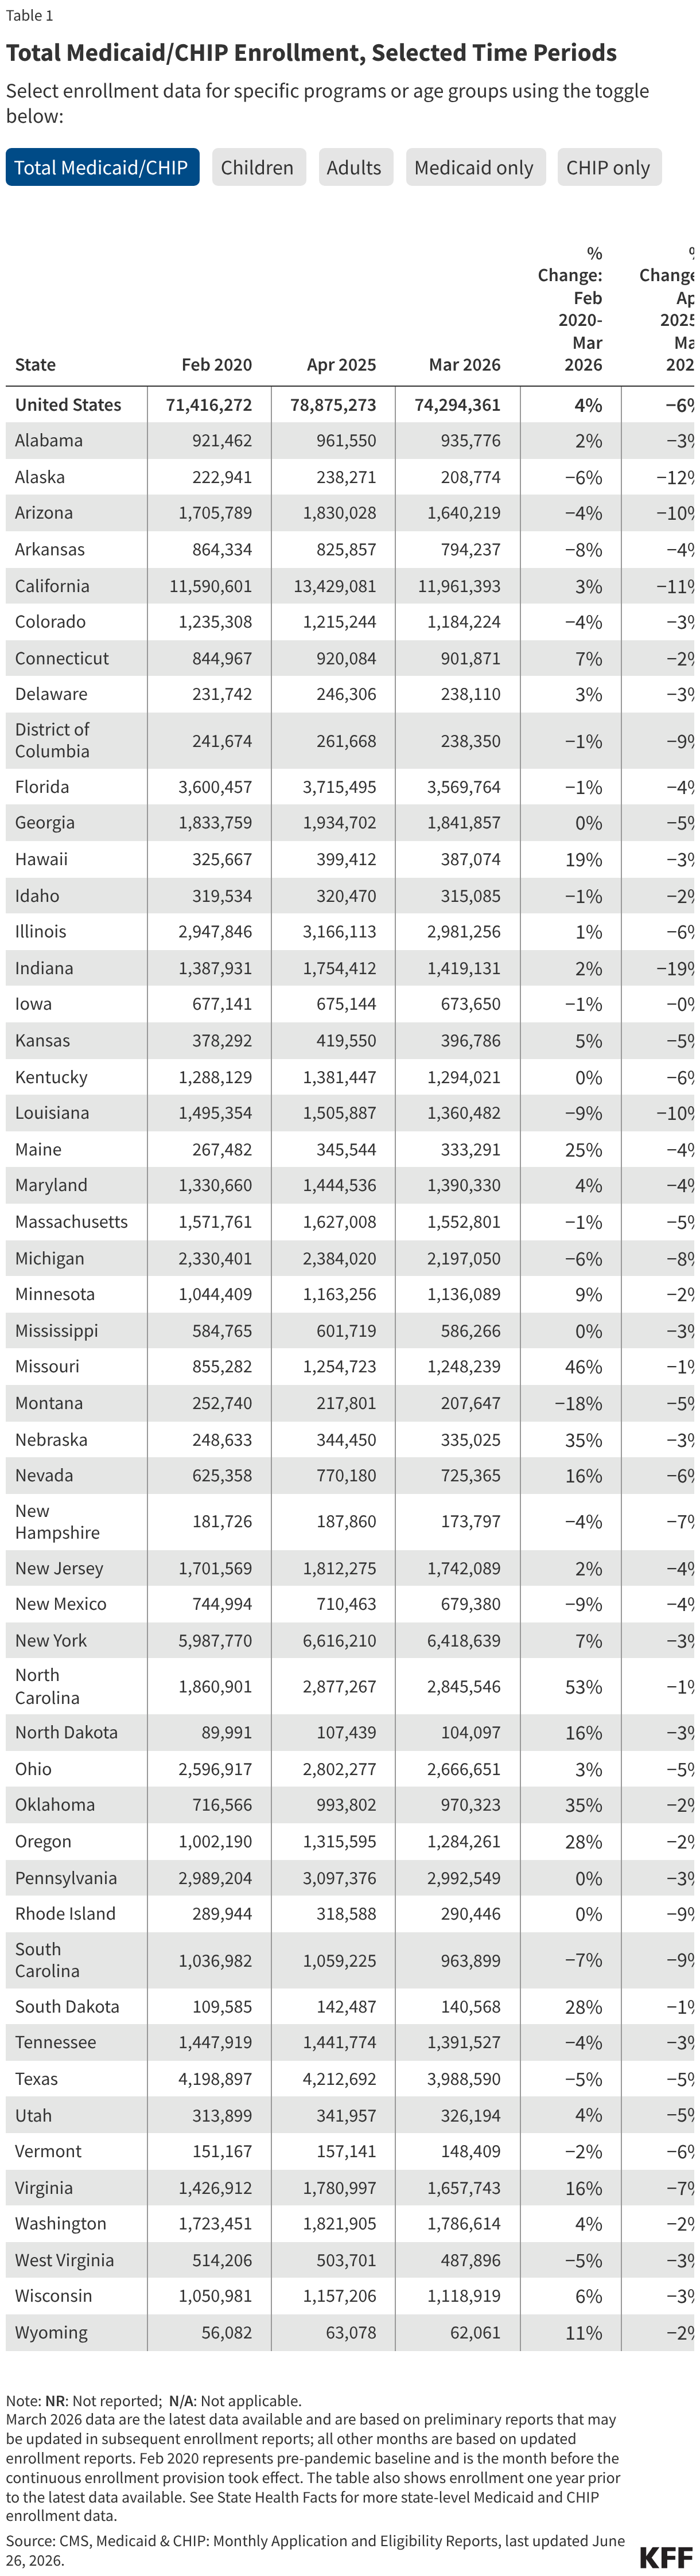
  • There were 73.5 million people enrolled in Medicaid/CHIP nationally (Figure 1). Medicaid enrollment declined by 5 million or 6% from May 2025 through May 2026 (Table 1).
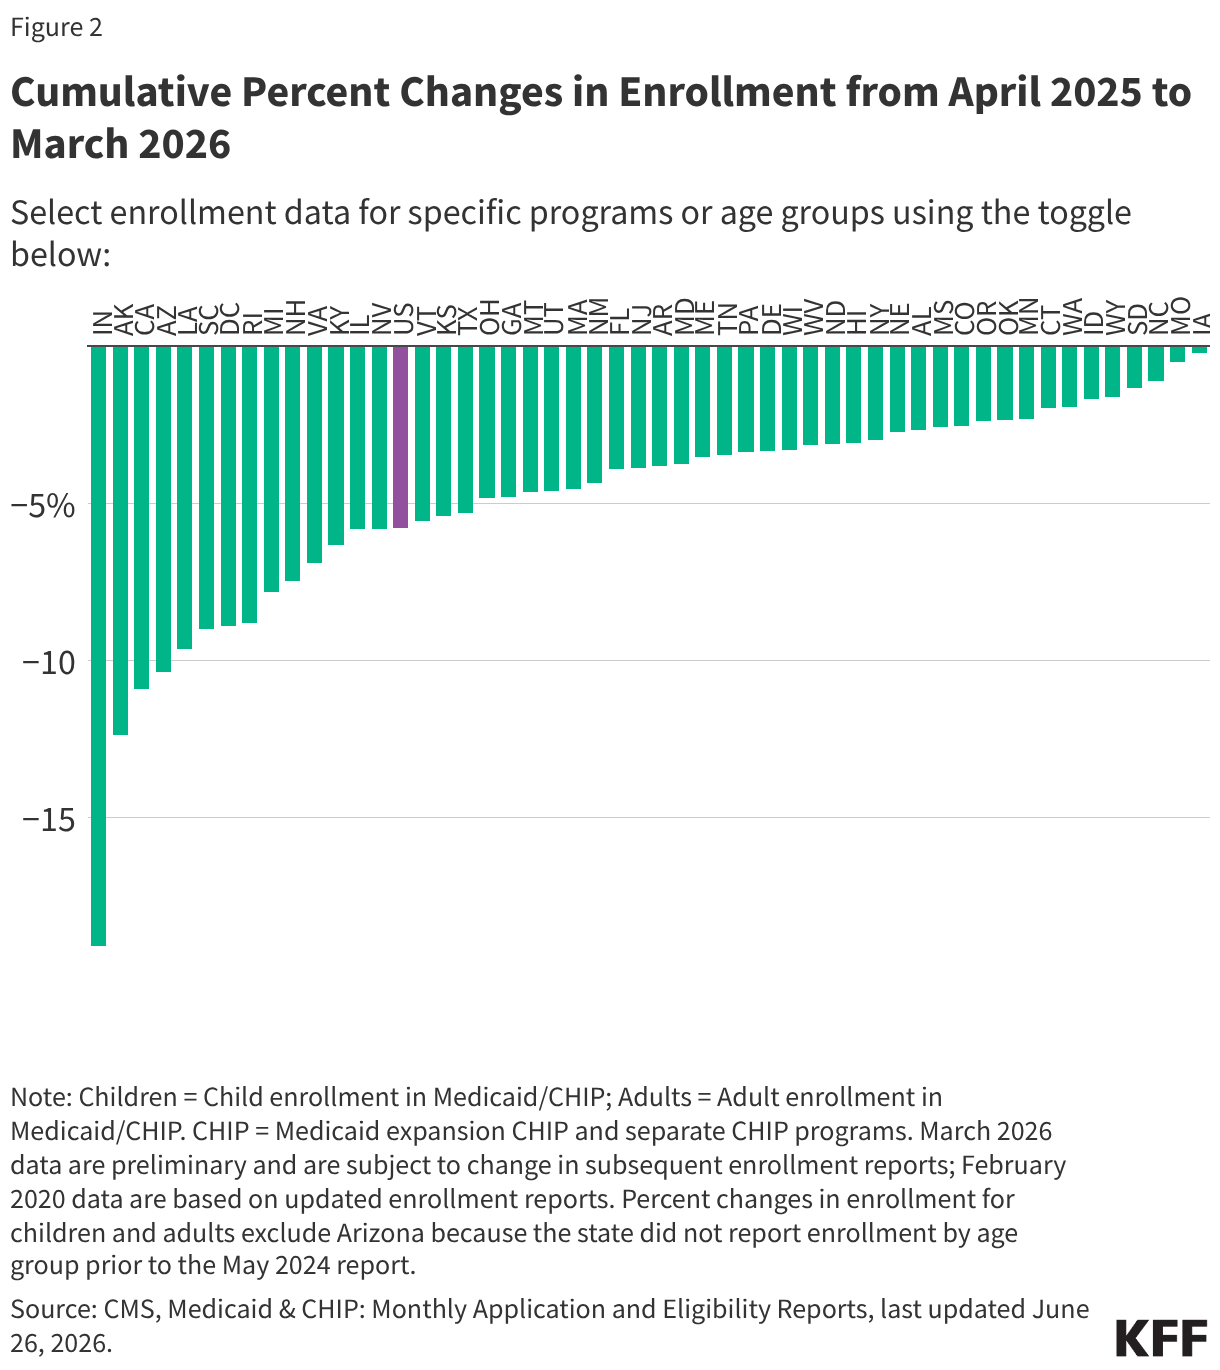
  • Total Medicaid/CHIP enrollment has decreased in 49 states and DC since May 2025. Enrollment changes since May 2025 vary from a less than 1% increase in Iowa to a 20% decrease in Indiana (Figure 2).
  • Child enrollment in Medicaid/CHIP has decreased in 49 states and DC from May 2025 through May 2026. Adult enrollment has decreased in all but five states (IA, MO, NC, OK, SD) (Figure 2).
  • There were 66.4 million people enrolled in Medicaid and 7.1 million people enrolled in CHIP (Figure 1). Since May 2025, Medicaid enrollment has decreased in 49 states and DC while CHIP enrollment has increased in 21 states (AL, CA, CT, DE, FL, HI, IL, MO, NE, NJ, NM, NC, ND, OK, RI, SC, TN, VT, WA, WI, WY).
  • Total Medicaid/CHIP enrollment was 3% higher in May 2026 compared to enrollment in February 2020, prior to the pandemic. However, in the 49 states and DC with complete enrollment data by age, the number of children enrolled in Medicaid/CHIP declined by 789,000 or 2% from February 2020 to May 2026 (Figure 2 and Table 1).
Figure 1
Annual Percent Change in Medicaid/CHIP Enrollment (May 2025 to May 2026) (Column Chart)
Total Medicaid/CHIP Enrollment, Selected Time Periods (Table)

Note: The data on unwinding renewal outcomes presented below were last updated on September 12, 2024; since most states have now completed the Medicaid unwinding, the information will not be updated again.

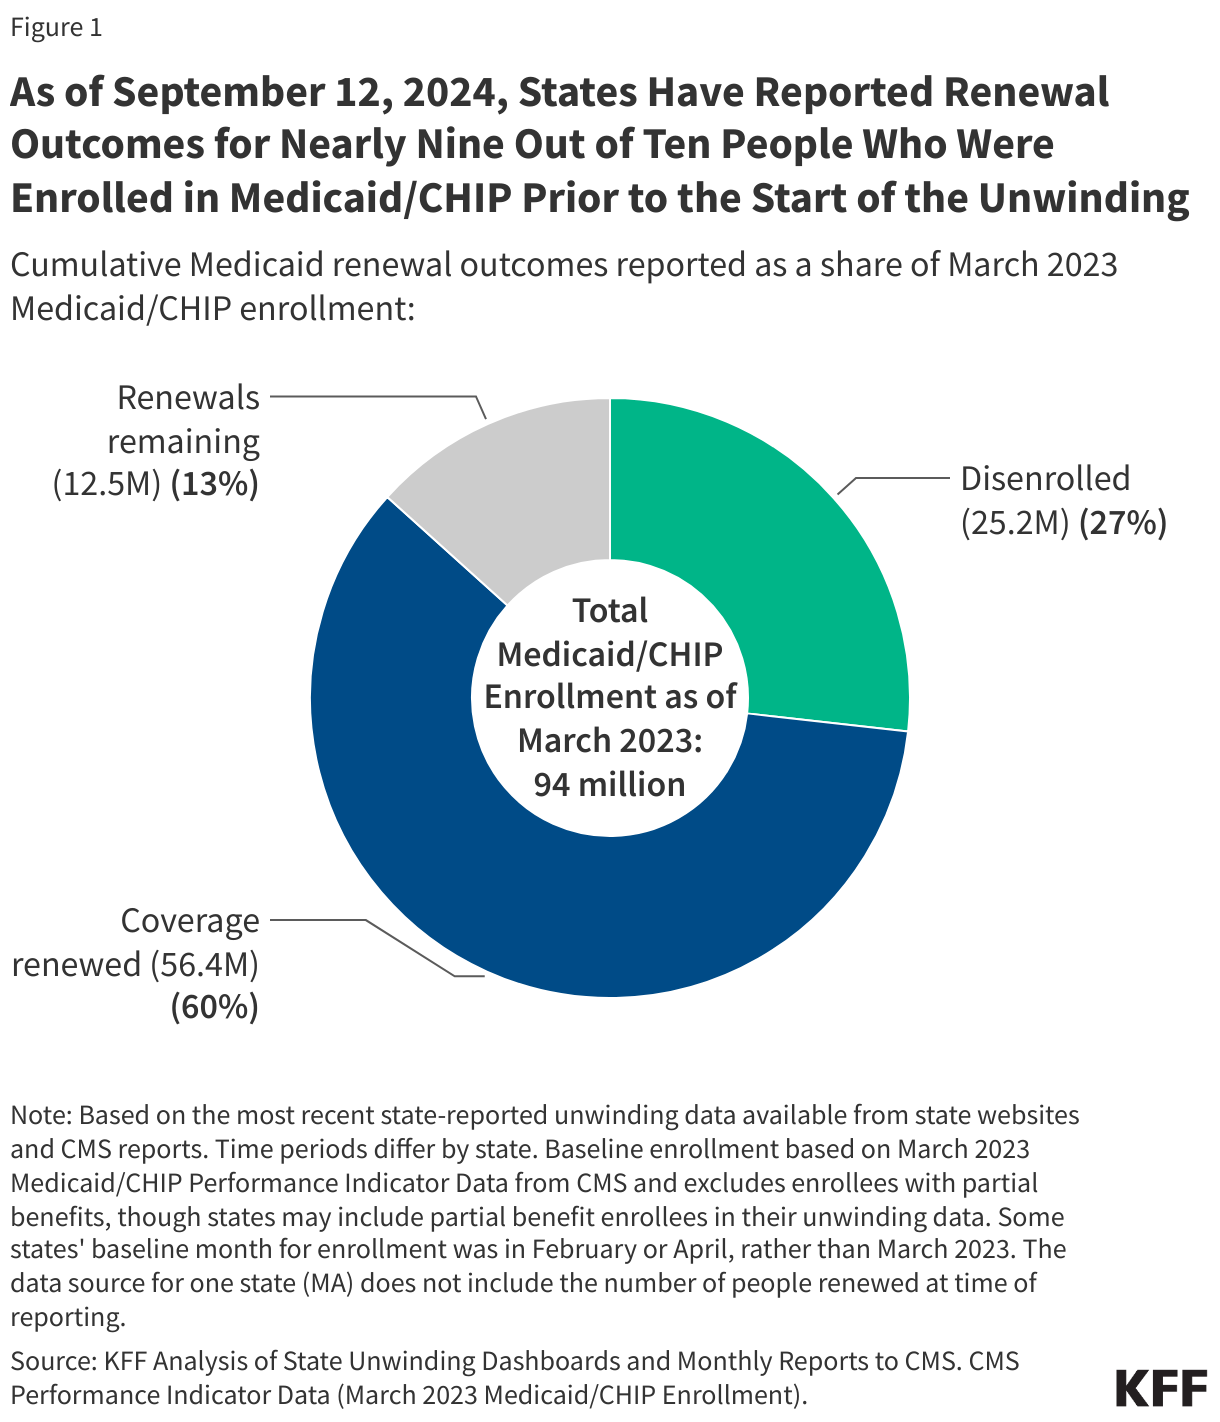
As of September 12, 2024 and with nearly complete unwinding data for most states: 

  • Over 25 million people were disenrolled (31% of completed renewals) and over 56 million people had their coverage renewed (69% of completed renewals).  
  • Disenrollment rates varied across states from 57% in Montana to 12% in North Carolina, driven by a variety of factors including differences in renewal policies and procedures as well as eligibility expansions in some states.  
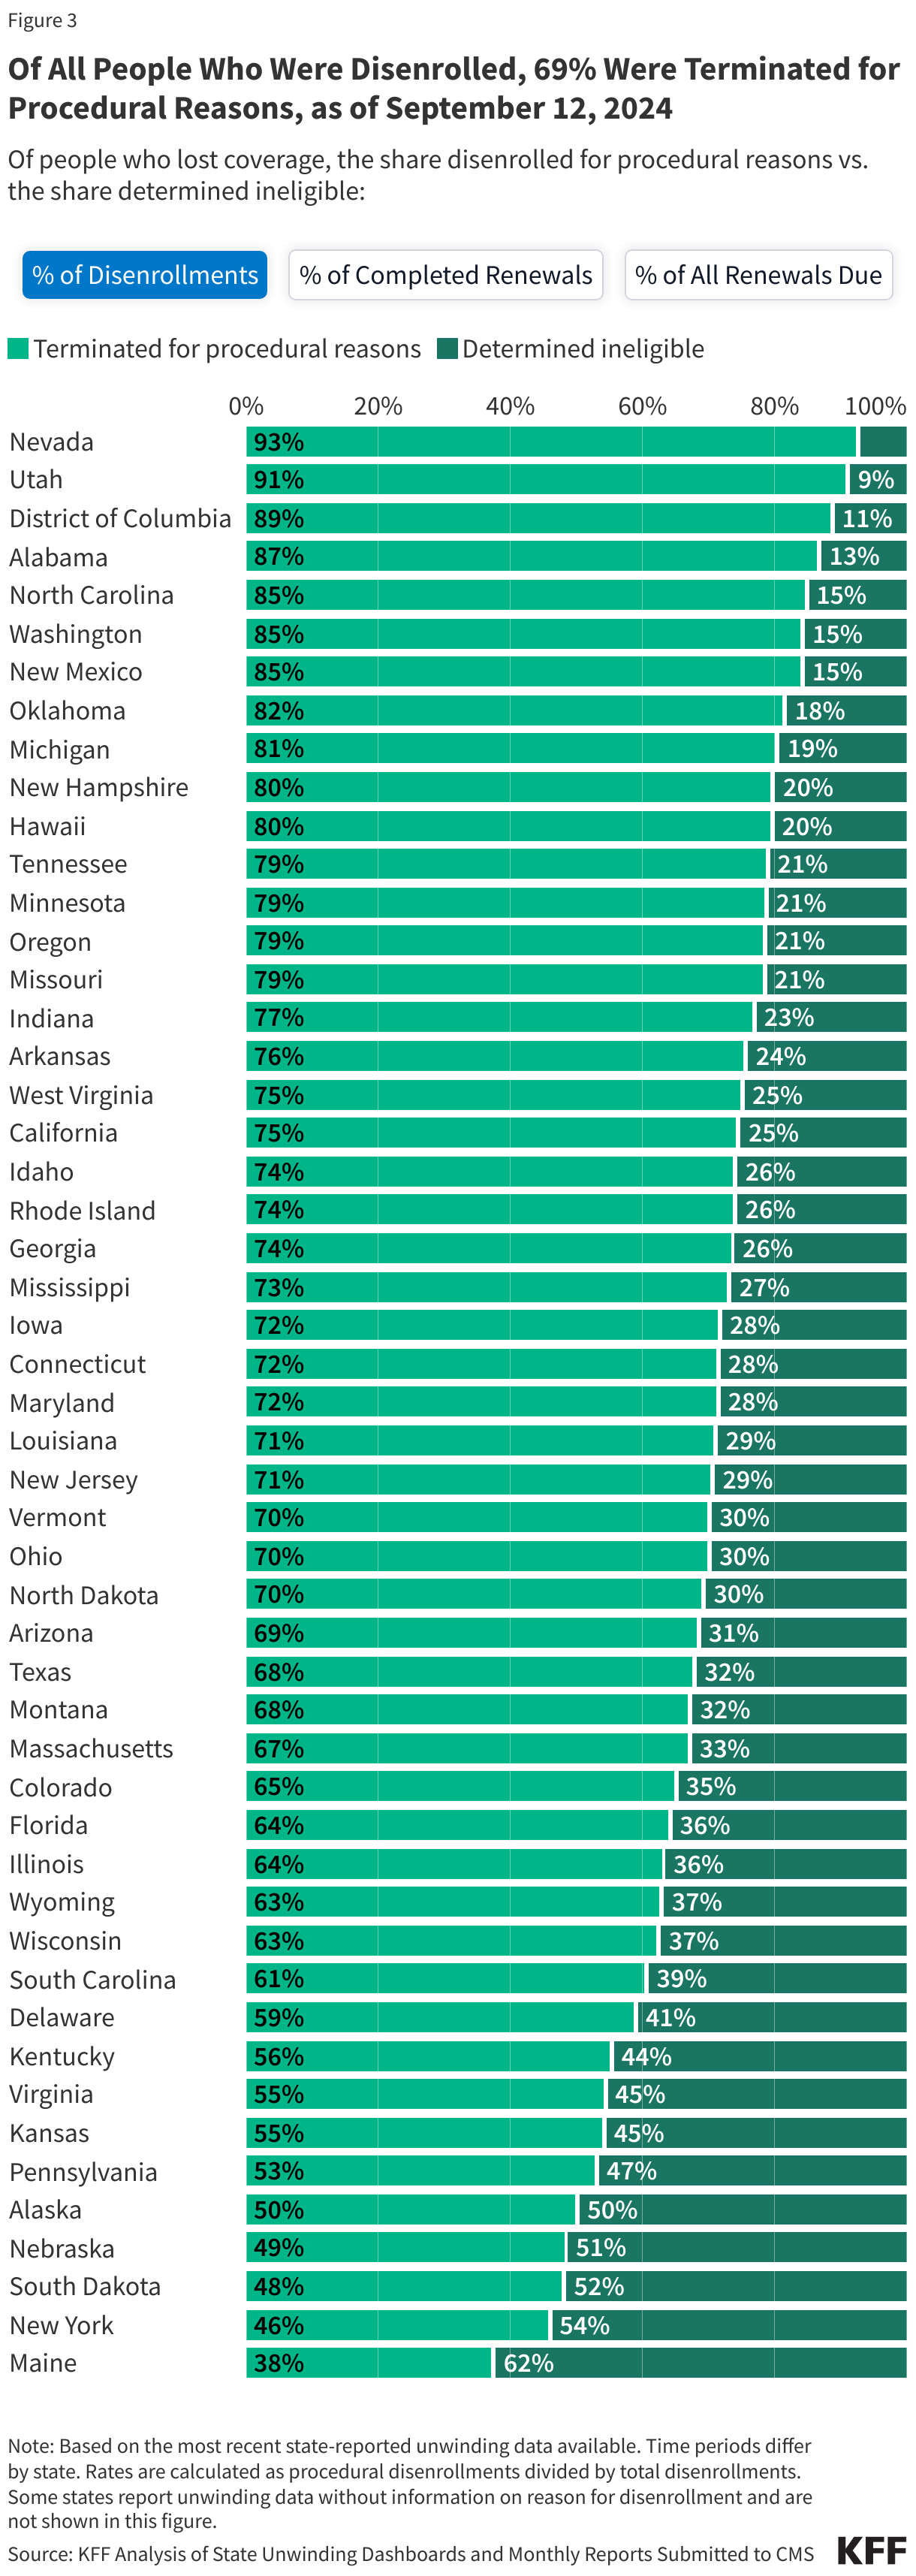
  • Among those who were disenrolled, nearly seven in ten (69%) were disenrolled for paperwork or procedural reasons while three in ten (31%) were determined ineligible.  
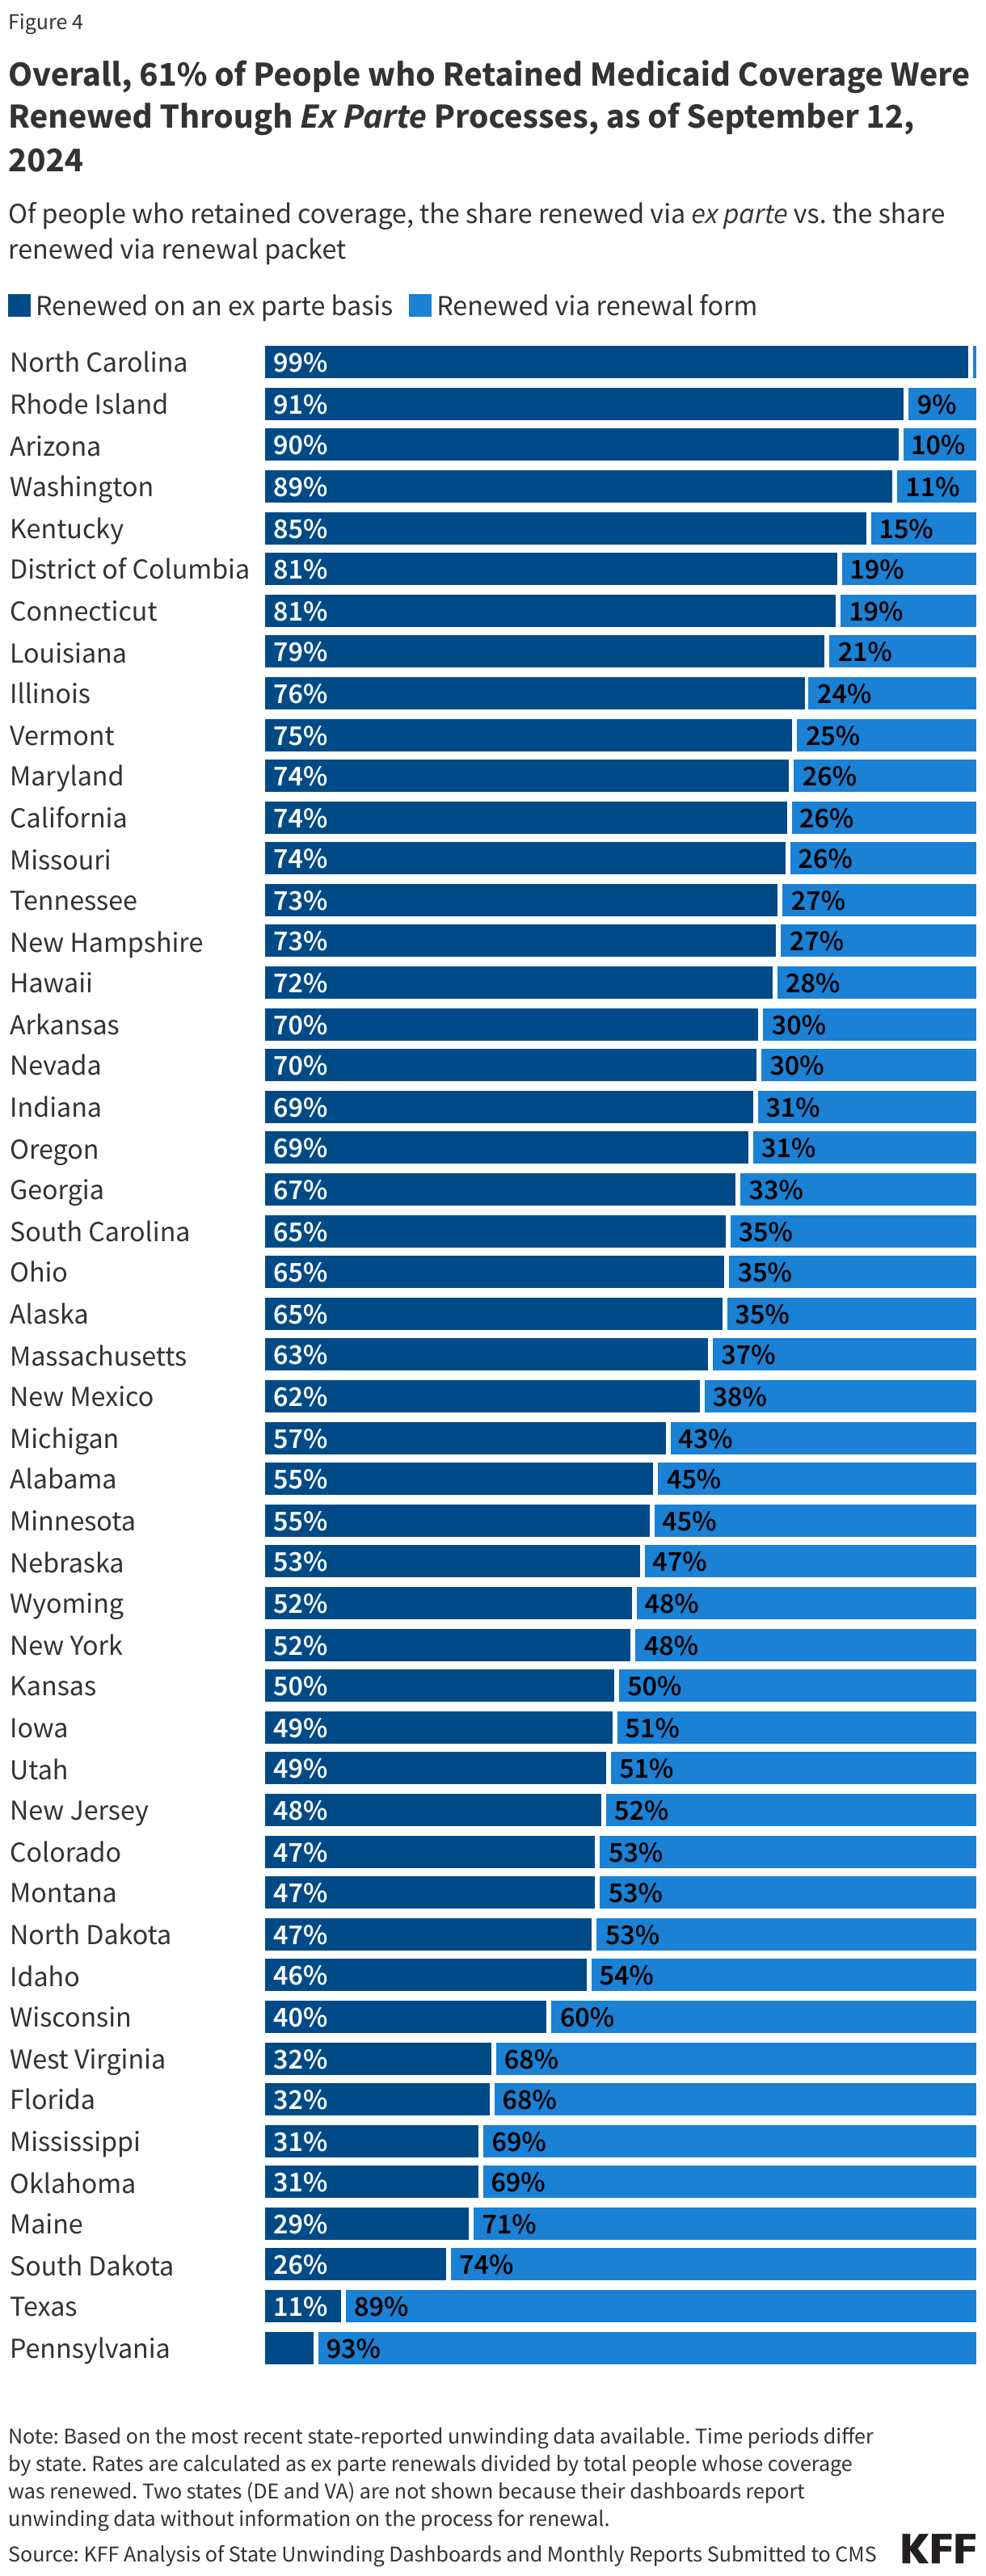
  • Among those whose coverage was renewed during the unwinding, 61% were renewed on an ex parte, or automated, basis, meaning the individual did not have to take any action to maintain coverage. 

State Data on Renewal Outcomes

The data on unwinding-related renewal outcomes presented in this section rely primarily on monthly reports that states were required to submit to the Centers for Medicare & Medicaid Services (CMS) during the unwinding period. The data also reflect updates to the monthly reports that states submit three months after the original report submission to account for the resolution of pending cases and any other changes in renewal metrics. For 13 states, data were pulled from dashboards or reports published on state websites that provide more complete information, and for a few additional states, updated monthly reports were pulled from state websites because they were more timely than what is reported on the CMS website. 

To view archived data for specific states, click on the State Data - Archived tab.


As of September 12, 2024, States Have Reported Renewal Outcomes for Nearly Nine Out of Ten People Who Were Enrolled in Medicaid/CHIP Prior to the Start of the Unwinding (Donut Chart)


Medicaid Disenrollments

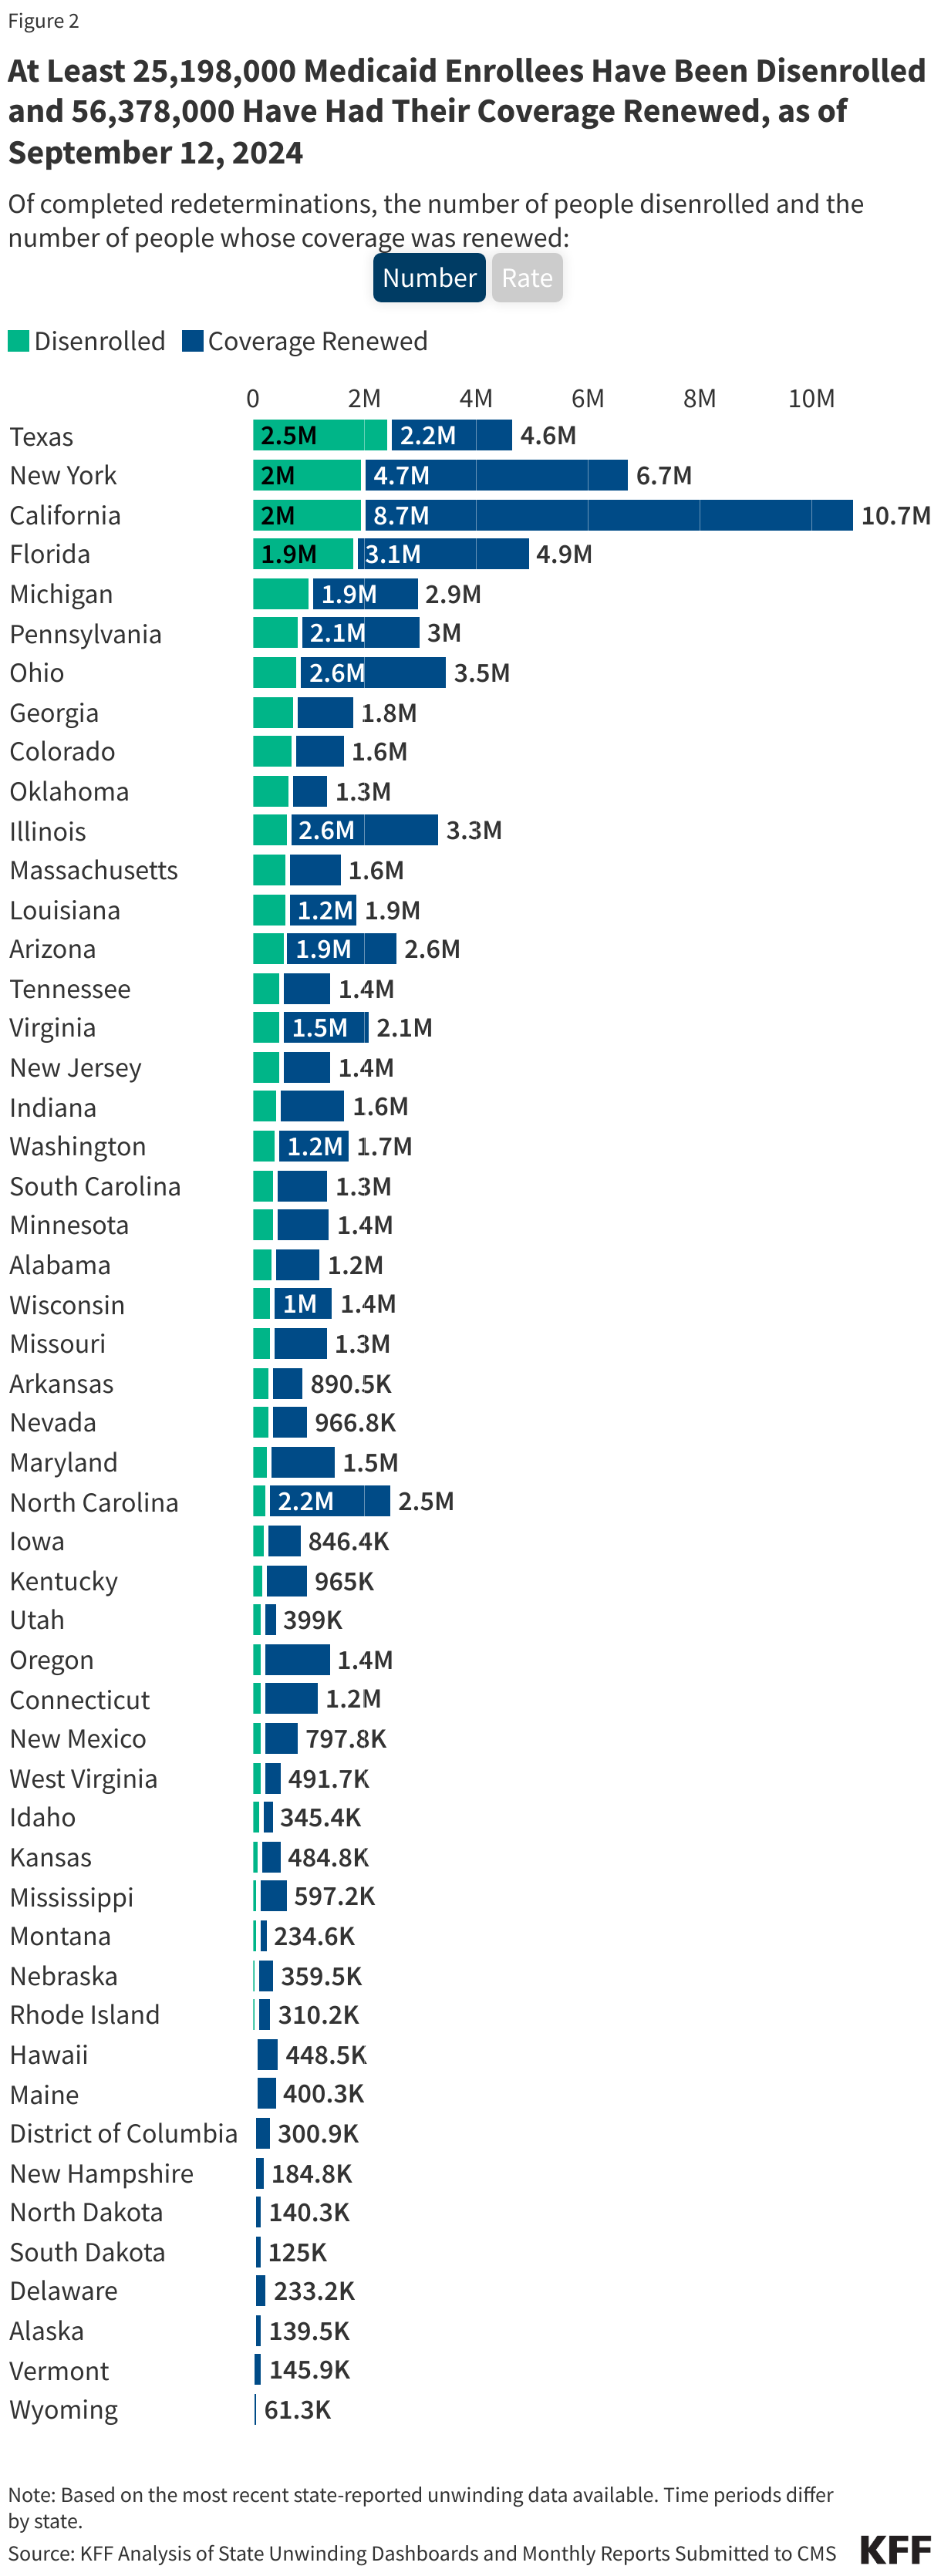
  • As of September 12, 2024, at least 25,198,000 Medicaid enrollees had been disenrolled during the unwinding of the continuous enrollment provision. Overall, 31% of people with a completed renewal were disenrolled in reporting states while 69%, or 56.4 million enrollees, had their coverage renewed.
  • There is wide variation in disenrollment rates across reporting states, ranging from 57% in Montana to 12% in North Carolina. A variety of factors contribute to these differences, including differences in renewal policies and system capacity. Some states adopted policies that promote continued coverage among those who remain eligible and/or have automated eligibility systems that can more easily and accurately process renewals while other states have adopted fewer of these policies and have more manually-driven systems. In addition, North Carolina and South Dakota adopted Medicaid expansion and other states increased eligibility levels for certain populations (e.g., children, parents, etc.) during the unwinding, which may have lowered disenrollment rates in these states.

At Least 25,198,000 Medicaid Enrollees Have Been Disenrolled and 56,378,000 Have Had Their Coverage Renewed, as of September 12, 2024 (Stacked Bars)


  • Across all states with available data, 69% of all people disenrolled had their coverage terminated for procedural reasons. However, these rates vary based on how they are calculated (see note below). Procedural disenrollments are cases where people are disenrolled because they did not complete the renewal process and can occur when the state has outdated contact information or because the enrollee does not understand or otherwise does not complete renewal packets within a specific timeframe. High procedural disenrollment rates are concerning because many people who are disenrolled for these paperwork reasons may still be eligible for Medicaid coverage. 

(Note: The first tab in the figure below calculates procedural disenrollment rates using total disenrollments as the denominator. The second tab shows these rates using total completed renewals, which include people whose coverage was terminated as well as those whose coverage was renewed, as the denominator. And finally, the third tab calculates the rates as a share of all renewals due, which include completed renewals and pending cases.)

Of All People Who Were Disenrolled, 69% Were Terminated for Procedural Reasons, as of September 12, 2024 (Stacked Bars)

Medicaid Renewals

  • Of the people whose coverage has been renewed as of September 12, 2024, 61% were renewed on an ex parte basis while 39% were renewed through a renewal form, though rates vary across states. Under federal rules, states are required to first try to complete administrative (or “ex parte”) renewals by verifying ongoing eligibility through available data sources, such as state wage databases, before sending a renewal form or requesting documentation from an enrollee. Ex parte renewal rates varied across states from 90% or more in Arizona, North Carolina, and Rhode Island to less than 20% in Pennsylvania and Texas. 

Overall, 61% of People who Retained Medicaid Coverage Were Renewed Through Ex Parte Processes, as of September 12, 2024 (Stacked Bars)

Federal Data on Renewal Outcomes

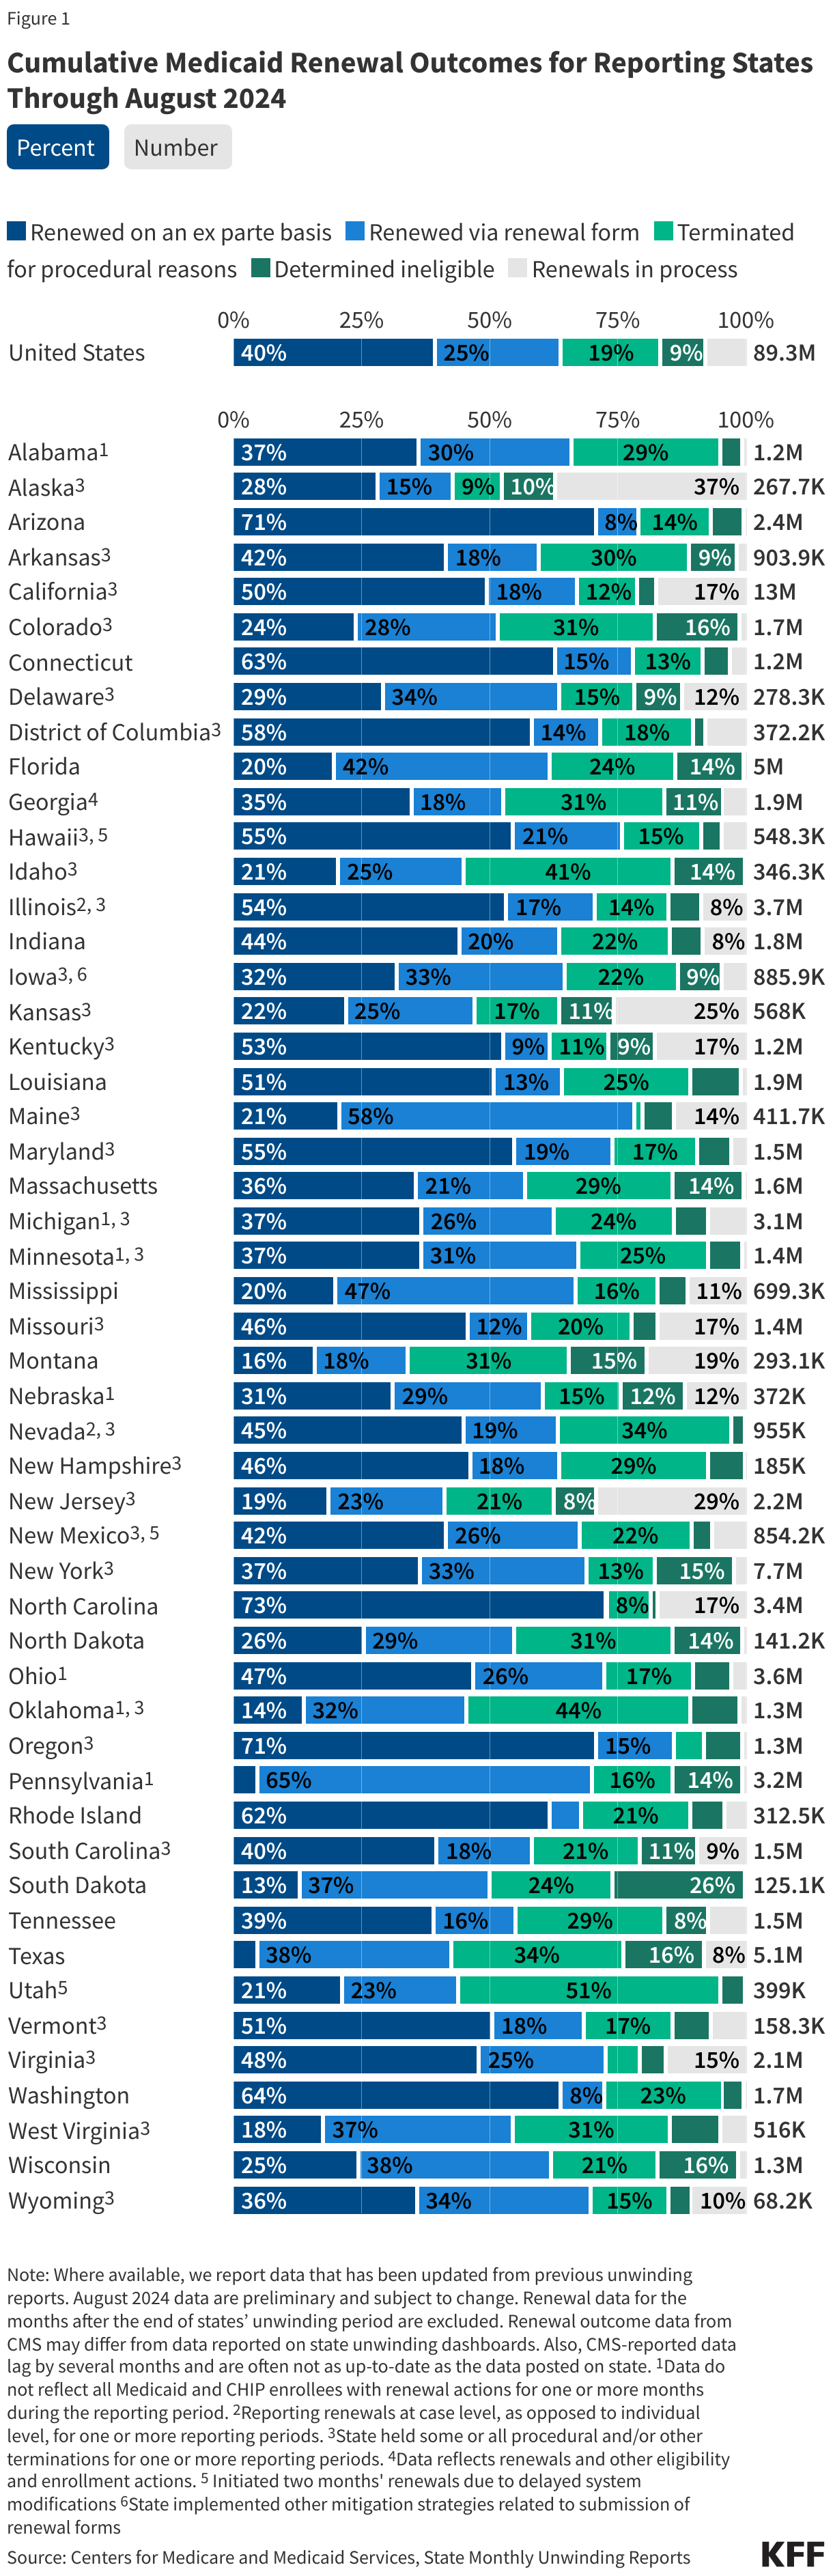
The data presented here are cumulative unwinding metrics published by CMS. These counts and percentages may differ from the above data, which present renewal metrics reported on state websites when state-reported data are more complete.  

Figure 1 below shows cumulative renewal data reported by CMS during states’ unwinding periods. Renewal data for the months after the end of states’ unwinding period are excluded. The data reflect updated unwinding data reported by states three months after the original monthly reports as they become available.   

Cumulative Medicaid Renewal Outcomes for Reporting States Through August 2024 (Stacked Bars)

For questions about this tracker, please contact KFFTracker@kff.org

State Unwinding Data - Archived

Note: The state data presented below were last updated on September 12, 2024; since most states have now completed the Medicaid unwinding, the information will not be updated again. 

The data presented here provide state-level data on enrollment trends and renewal outcomes during the unwinding period. Figure 1 shows total Medicaid enrollment by month starting in January 2023 and, once disenrollments resumed in a state, the cumulative percent change in Medicaid enrollment relative to the month before Medicaid disenrollments started (this baseline month will differ across states). Figure 2 shows renewal metrics for each month of a state’s unwinding period (or cumulative data for the unwinding period for some states). 

For total national Medicaid enrollment, click on the Enrollment Data tab.

Related Resources - Archived

Resources on unwinding data

Resources on state policies and preparations for the unwinding

Resources on pre-pandemic enrollment patterns and coverage transitions

KFF’s unwinding explainer

The Business of Health with Chip Kahn

AI’s Role in Health Care: What Keeps You Up at Night?

September 8, 2026

Video

Audio

About this Episode


Episode 14, AI Series: At the close of every episode, Chip asks his guests the same question: ‘What keeps you up at night?’ In this highlights episode, we share intriguing responses on AI’s role in health care. From deepfakes and misinformation to bias and the risk of losing the human connection at the heart of care, these highlights capture some of the top issues today.

The Host


Headshot photo of Chip Kahn wearing a navy blue suit with a red tie, red pendant on lapel, and glasses.

Sr. Visiting Fellow

Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.


SERIES

This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.

The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.

KFF Survey Methodology & Data Collection Standards

Published: Aug 28, 2026

About Our Surveys

 KFF has a long history of conducting public opinion polls to amplify the public’s voice in policy debates, including groups that are under-researched and under-reported. For the past three decades, KFF’s polling work has combined both rigorous methodology and transparency. Every survey we publish is accompanied by a full methodology statement and topline results, so readers can see details about how the data was collected, read every question included in the survey in the order in which they were asked, and judge its quality for themselves.  

 While asking the public about political issues and candidates is an important part of our polling work, KFF does not conduct “horse race” polling with the goal of predicting election outcomes. Our election-related polling focuses on how the public thinks about health care issues when making voting decisions, not on forecasting who might win.  While certain things about our survey methods change from project to project, the principles of our methodology are consistent and described below. To find more details for each survey, check out the “Topline & Methodology” link at the top right of each survey project on our website. 

How We Reach People 

 KFF surveys rely almost exclusively on probability-based sampling, meaning respondents are selected at random rather than choosing to participate on their own. Most of our national population surveys use a sampling approach that combines two sample types: 1) a probability-based panel and 2) a random digit dial sample of pre-paid cell phone numbers.  

 Probability-based panel members are recruited through random sampling, using two main methods: mailed invitations sent to addresses randomly selected from U.S. Postal Service delivery records, and random digit dialing of cell phone numbers. This means that, in principle, every U.S. adult has a known chance of being invited to join the panel, whether or not they were looking to take a survey. Once someone joins the panel, they can complete our surveys online, by phone, or in some cases by text message invitation to a web survey. This hybrid approach helps us reach people who might otherwise be left out of an online-only survey, including older adults, people with lower incomes, and people without reliable internet access. KFF works with multiple probability-based panels including the SSRS Opinion Panel, Ipsos Knowledge Panels, and NORC AmeriSpeak.  

For most projects, we supplement probability-based panels with a sample of random digit dialed pre-paid cell phone numbers. Pre-paid or “pay as you go” cell phone numbers are used disproportionately by population groups that respond at lower rates to traditional survey methods, including young Black and Hispanic men, and people who do not speak English. Combining these sample types helps our surveys be more representative of the diversity of the national population, not just those who are easiest to reach.  

Our national survey projects are conducted in English and Spanish, usually fielded over 5-6 days so people have more time to respond, and provide small financial incentives for individuals who participate, to help bring in those who might otherwise skip a survey. Without these steps, surveys run the risk of overrepresenting the most engaged or opinionated members of the public.   

In addition, KFF conducts deeper surveys on populations that general population polling cannot adequately capture. These projects start from the same principle as our general population surveys: probability-based sampling, whether through probability-based panels, address-based recruitment, voter registration lists, or purpose-built panels of previous respondents, adapted to fit the population being studied. Reaching a small, specific, or hard-to-reach group often requires fielding a survey in more languages, using more modes of contact, and longer field periods. 

How We Work To Be Representative 

Even with a well-designed sampling frame, most polls will not perfectly mirror the population on every characteristic, so we use statistical techniques to adjust, or weight, the results to align with known population benchmarks from sources like the Census Bureau on measures such as age, gender, race and ethnicity, education, and region. Weighting corrects for the fact that some groups are easier to reach than others and helps ensure that no single group is overrepresented or underrepresented in the final results.  

All KFF survey reports include margins of sampling error for the total sample and key subgroups, which reflect the statistical uncertainty that comes with asking questions of a sample rather than every single member of the population. In addition to sampling error, all public opinion polls may be subject to other types of error such as question wording effects, nonresponse bias, or mode effects.  

Our Polling Expertise and News Partnerships 

KFF has a team of polling experts who design our surveys, write questionnaires, analyze data, and write reports. This team works closely with KFF health policy experts who contribute their knowledge on issues like health reform, ACA, Medicare, Medicaid, women’s health, global health, and other issues to the survey design and reporting process.  

We don’t commission others to conduct polling on our behalf or undertake surveys on behalf of other organizations. We contract with outside organizations to perform survey fieldwork and statistical weighting, which is paid for through KFF’s endowment and sometimes using funds from outside funders. KFF maintains full editorial control over all its policy analysis, polling, and journalism activities, regardless of funding source. 

Some of our surveys are conducted in partnership with major news organizations in order to help KFF magnify its polling by combining survey data with in-depth journalism and storytelling, an approach that KFF has used since 1995. KFF and its partners choose survey topics together and design the survey instrument with input from both organizations while retaining full editorial independence over what each organization publishes. 

Artificial Intelligence in Survey Research 

KFF uses Artificial Intelligence (AI) in specific ways to strengthen our work and we publicly disclose when we’ve used AI in a way that is central to our survey methods. For example, we often use AI tools (with human oversight) to assist with coding of open-ended survey responses into discrete categories. KFF does not use AI to create or model “synthetic” public opinion. Every survey we field is grounded in real interviews with human respondents, selected through probability-based sampling, never generated, simulated, or estimated by AI standing in for actual human answers. 

Our Commitment to Methodological Transparency

KFF public opinion and survey research is a charter member of AAPOR’s Transparency Initiative. The American Association for Public Opinion Research (AAPOR) Code of Professional Ethics and Practices commits members to maintain the highest standards of scientific competence, integrity, accountability, and transparency in designing, conducting, analyzing, and reporting their work, and requires researchers to disclose sufficient information about how the research was conducted to allow for independent review and verification of research claims, regardless of the methodology used. 

Excellent survey research is not just about getting people to answer questions, it is about making sure the estimates are representative, can hold up to scrutiny, and are collected in a way that respects the people who take the time to answer. As trust in institutions, including in survey research itself, continues to decline, KFF remains committed to the methods that have proven most reliable over decades of public opinion research: random selection, careful weighting, and full transparency about how the work gets done. Reach out if you have any questions about our polls or our methodology. 


Poll Finding

Examining LGBTQ+ Adults’ Experiences with Health Care Costs and Access

Published: Aug 27, 2026

Key Takeaways

  • LGBTQ+ adults face significantly greater challenges accessing and affording health care compared to their non-LGBTQ+ peers. They are more likely to postpone or skip needed care (58% vs. 38%), forgo prescription medications due to cost (22% vs. 12%), and struggle to pay medical bills (30% vs. 21%).
  • Cost-related barriers to care are especially pronounced among certain segments of the LGBTQ+ population, most notably trans adults, younger LGBTQ+ adults, those with lower incomes, and those without health coverage. Eight in ten (82%) trans adults, three-quarters (77%) of LGBTQ+ adults without health coverage, and two-thirds (68%) of those under age 30 report not getting needed health care in the past 12 months either because they couldn’t get an appointment, couldn’t afford the cost, or for another reason. Additionally, larger shares of LGBQ+ women than men report skipping or delaying care in the past year (63% vs. 46%).
  • While trans adults represent a small share of the total LGBTQ+ population, they experience outsized barriers to affording care and other access issues. Compared with other LGBQ+ groups, trans adults report the highest rates of difficulty finding providers with available appointments (53%), not taking prescription medications because of cost (39%), worsening health from postponed care (45%), struggling with medical bills (42%), and experiencing insurance delays or denials (61%). Trans adults experience these greater barriers to health cost and access even when controlling for other demographic variables such as age, income, and insurance status.
  • Health care costs create significant financial strain for many LGBTQ+ adults. Three in ten (30%) report problems paying medical bills in the past year, and one in five (19%) say they cut back on household necessities such as food or clothing to pay for health care costs. Financial burdens are particularly common among younger adults, those with lower incomes, and those without health coverage.
  • Having health insurance does not guarantee timely access to care. About three in ten LGBTQ+ insured adults report that their insurance delayed or denied coverage for recommended care in the past two years, a more widespread experience than among non-LGBTQ+ insured adults, with particularly high rates among trans adults and those covered by Medicaid or those with ACA marketplace coverage.

Understanding the Challenges LGBTQ+ Adults Face Affording Health Care

LGBTQ+ adults in the U.S. are a growing population who have historically faced health disparities in terms of both wellbeing and health care access and affordability. Previous research has found that LGBTQ+ adults are more likely than their non-LGBTQ+ peers to experience barriers to obtaining needed care, to struggle to afford health care costs, and to delay or forgo care because of cost. These affordability challenges often intersect with and may even be a driver of broader health disparities, including poorer mental and physical health outcomes, particularly among trans adults.

Understanding the financial challenges LGBTQ+ adults face when accessing health care can help identify persistent gaps in affordability and inform efforts to improve access to needed care and coverage.

LGBTQ+ definition and demographics

The LGBTQ+ sample included in this analysis is comprised of 2,640 adults, including 52% who identify as bisexual, 21% as gay men, 9% as lesbian women, 9% as transgender, and 9% who use some other term to identify themselves. The analysis is broken out by transgender (trans) adults (9%), lesbian, gay, bisexual or other queer identifying men (39%), and lesbian, gay, bisexual, or other queer identifying women (50%).

The LGBTQ+ community is not a monolith and beyond differences related to sexual orientation and gender identity, health care experiences can vary widely depending on age, income, and insurance status, among other factors. This analysis also examines differences by these factors. For example, regardless of LGBTQ+ identity, women tend to have more interactions with the health care system than men and therefore, may have more cost or access issues. In addition, trans adults are more likely than other groups to face barriers in health care, including discrimination and lack of providers trained to handle the health needs of trans adults. Subgroups of the LGBTQ+ population, including trans adults or older adults usually make up too small a share of national survey samples to allow for statistically reliable analysis. The large sample size of this survey provides a unique opportunity to examine these differences.

This report also compares the experiences of LGBTQ+ adults with their non-LGBTQ+ counterparts. A caveat to these comparisons is that there are key demographic differences between LGBTQ+ and non-LGBTQ+ adults that may contribute to differences in measures of health care cost and access between these populations. LGBTQ+ people are generally younger than the U.S. population overall, have lower incomes, and are somewhat more likely to be uninsured. Therefore, some findings might be more reflective of income or coverage differences, for example, than LGBTQ+ identity, though those factors are certainly intertwined. See appendix for a more detailed analysis of the demographic characteristics of the LGBTQ+ community.

Delays in Health Care for LGBTQ+ Adults

Six in ten LGBTQ+ adults (58%) say they have skipped or postponed needed health care in the past year, greater shares than their non-LGBTQ+ counterparts (38%). This includes more than four in ten (43%) LGBTQ+ adults who say they’ve skipped or delayed getting needed care because of the cost and about three in ten who said it was due to their inability to get an appointment (28%) or for some other reason (29%). LGBTQ+ adults are nearly twice as likely as non-LGBTQ+ adults (26%) to say they’ve skipped or delayed getting needed care because of the costs.

Compared to other LGBQ+ adults, trans adults are more likely to report they have put off care in the past year because of cost or other issues (82%). At least half of trans adults say they skipped or postponed getting needed health care because of the cost (56%), because they couldn’t find a doctor or health care provider with appointments available (53%), or they skipped or postponed for any other reasons (48%). There may be many reasons why trans adults are more likely to skip or delay care, but a recent KFF/Washington Post Trans Survey found significant barriers for trans adults in getting needed health care, including providers not being properly educated to provide appropriate care.

Beyond trans adults, larger shares of LGBQ+ women than men report skipping or postponing care in the past year (63% vs. 46%). This includes half of LGBQ+ women who say they skipped or postponed needed care because of the cost (compared to a third of LGBQ+ men), and roughly a third of LGBQ+ women who say they skipped or postponed care because they couldn’t get an appointment (31% vs. 19% of LGBQ+ men) or for any reason besides cost or not being able to get an appointment (32% vs. 21% of LGBQ+ men). Across all LGBTQ+ groups, non-LGBTQ+ adults less commonly reported skipping or postponing care.  

Many socioeconomic and demographic factors can predict delaying or skipping care, but LGBTQ+ adults are more likely to skip or delay care even when controlling for race and ethnicity, insurance coverage, age, income, and education, suggesting this population group may have unique struggles in accessing needed health care. The differences reported in this analysis between LGBTQ+ adults and non-LGBTQ+ adults hold even when controlling for these demographic characteristics.
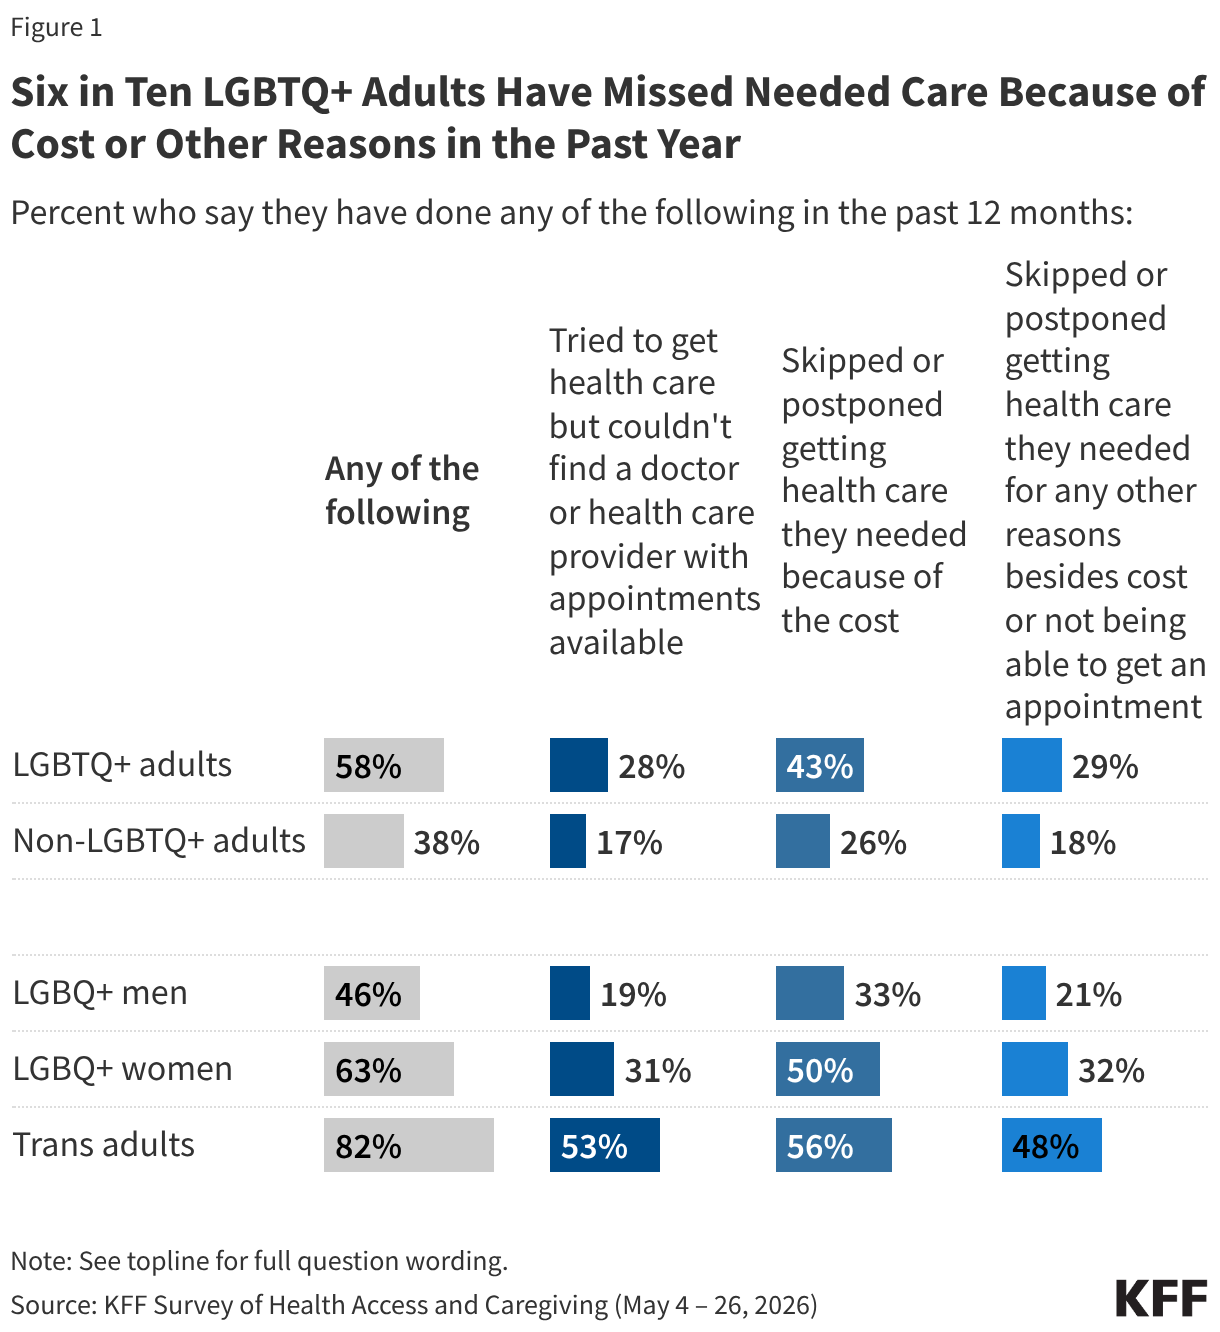
Six in Ten LGBTQ+ Adults Have Missed Needed Care Because of Cost or Other Reasons in the Past Year (Split Bars)

Among all LGBTQ+ adults, two-thirds (68%) of those under age 30 report having put off needed care in the past year, higher than the shares of older LGBTQ+ adults who report this. While age is a significant predictor of putting off care regardless of sexual identity, LGBTQ+ adults under age 30 are twenty percentage points more likely to report putting off care than non-LGBTQ+ adults in the same age range (48%). In fact, across most age groups, LGBTQ+ adults are more likely to report putting off or postponing needed care than their non-LGBTQ+ counterparts, except for those 65 and older. The difference between LGBTQ+ and non-LGBTQ+ adults levels out among those age 65 and older, which may be due to several factors, such as increased medical care among older adults and Medicare eligibility.
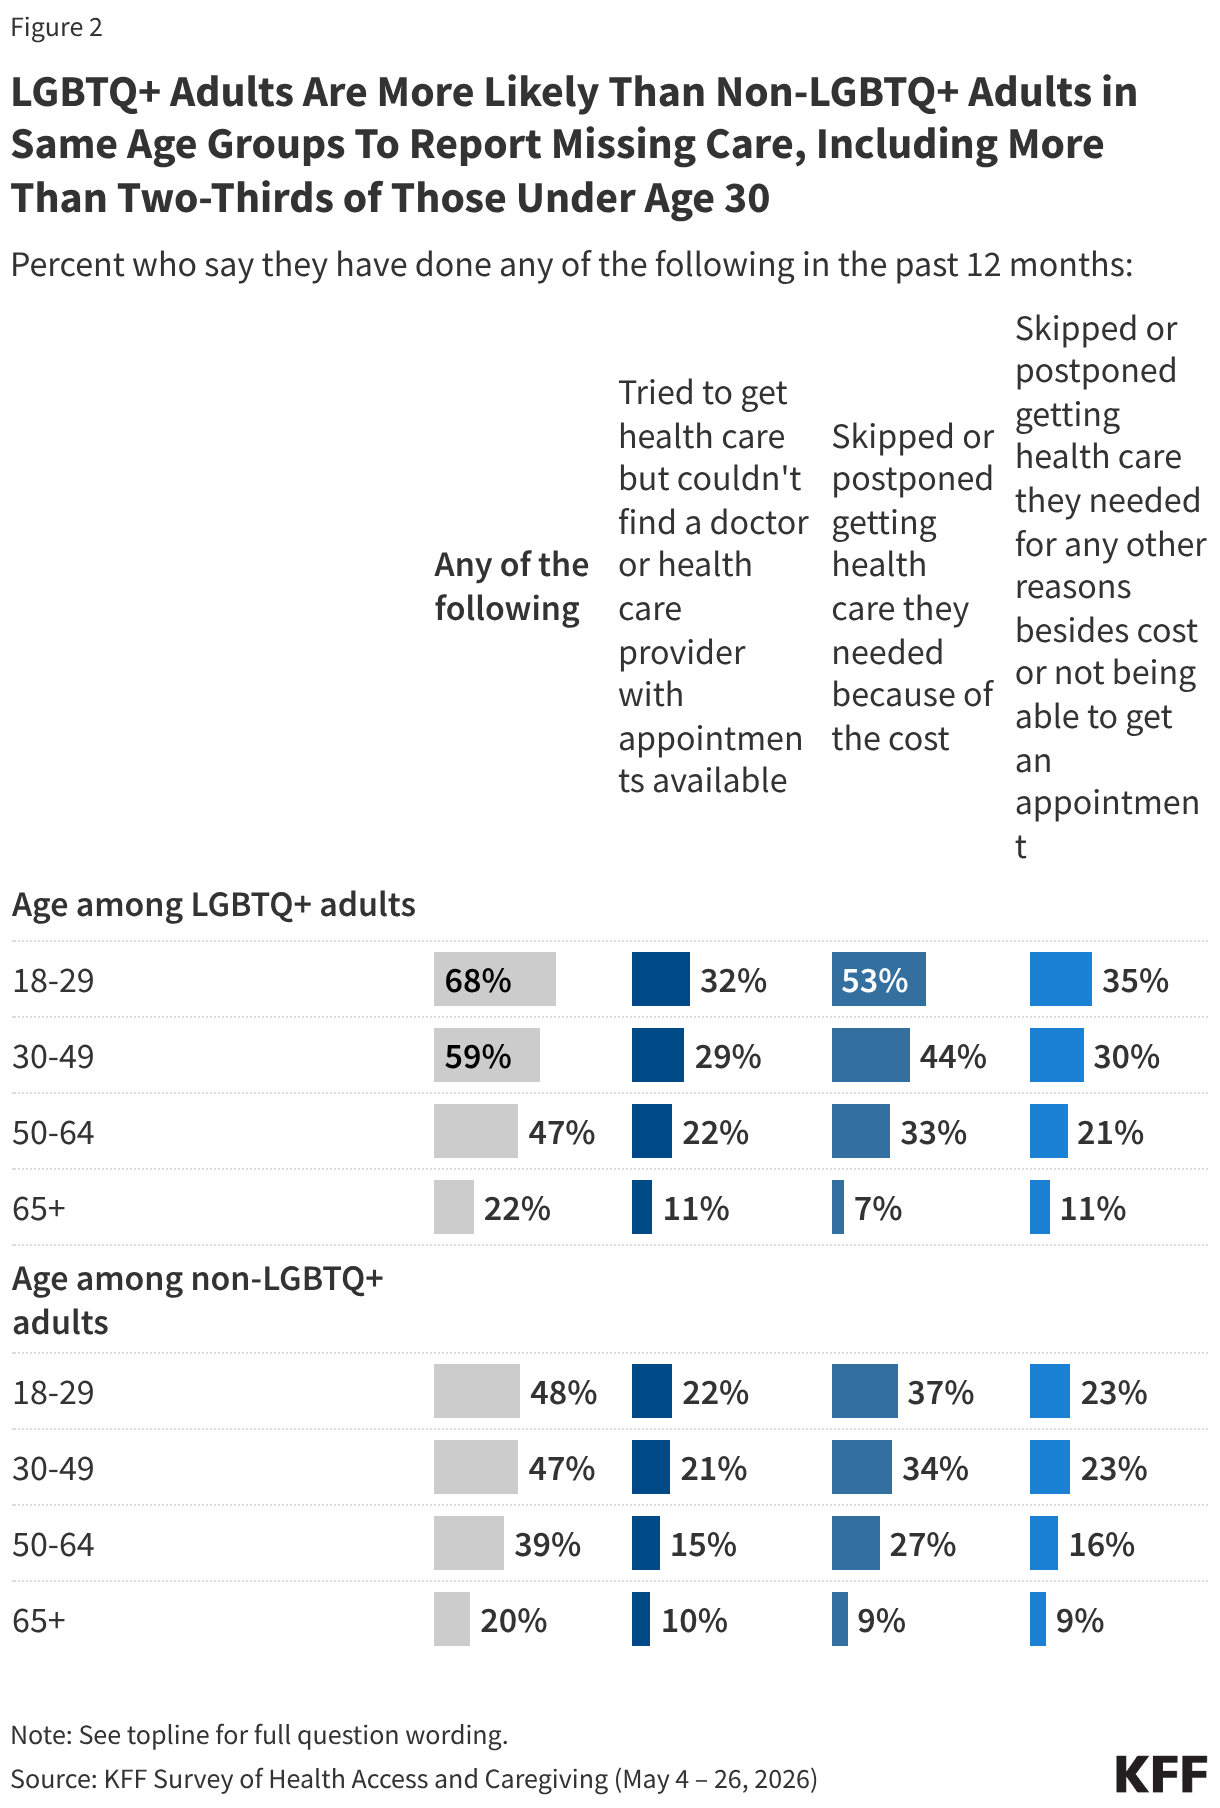
LGBTQ+ Adults Are More Likely Than Non-LGBTQ+ Adults in Same Age Groups To Report Missing Care, Including More Than Two-Thirds of Those Under Age 30 (Split Bars)

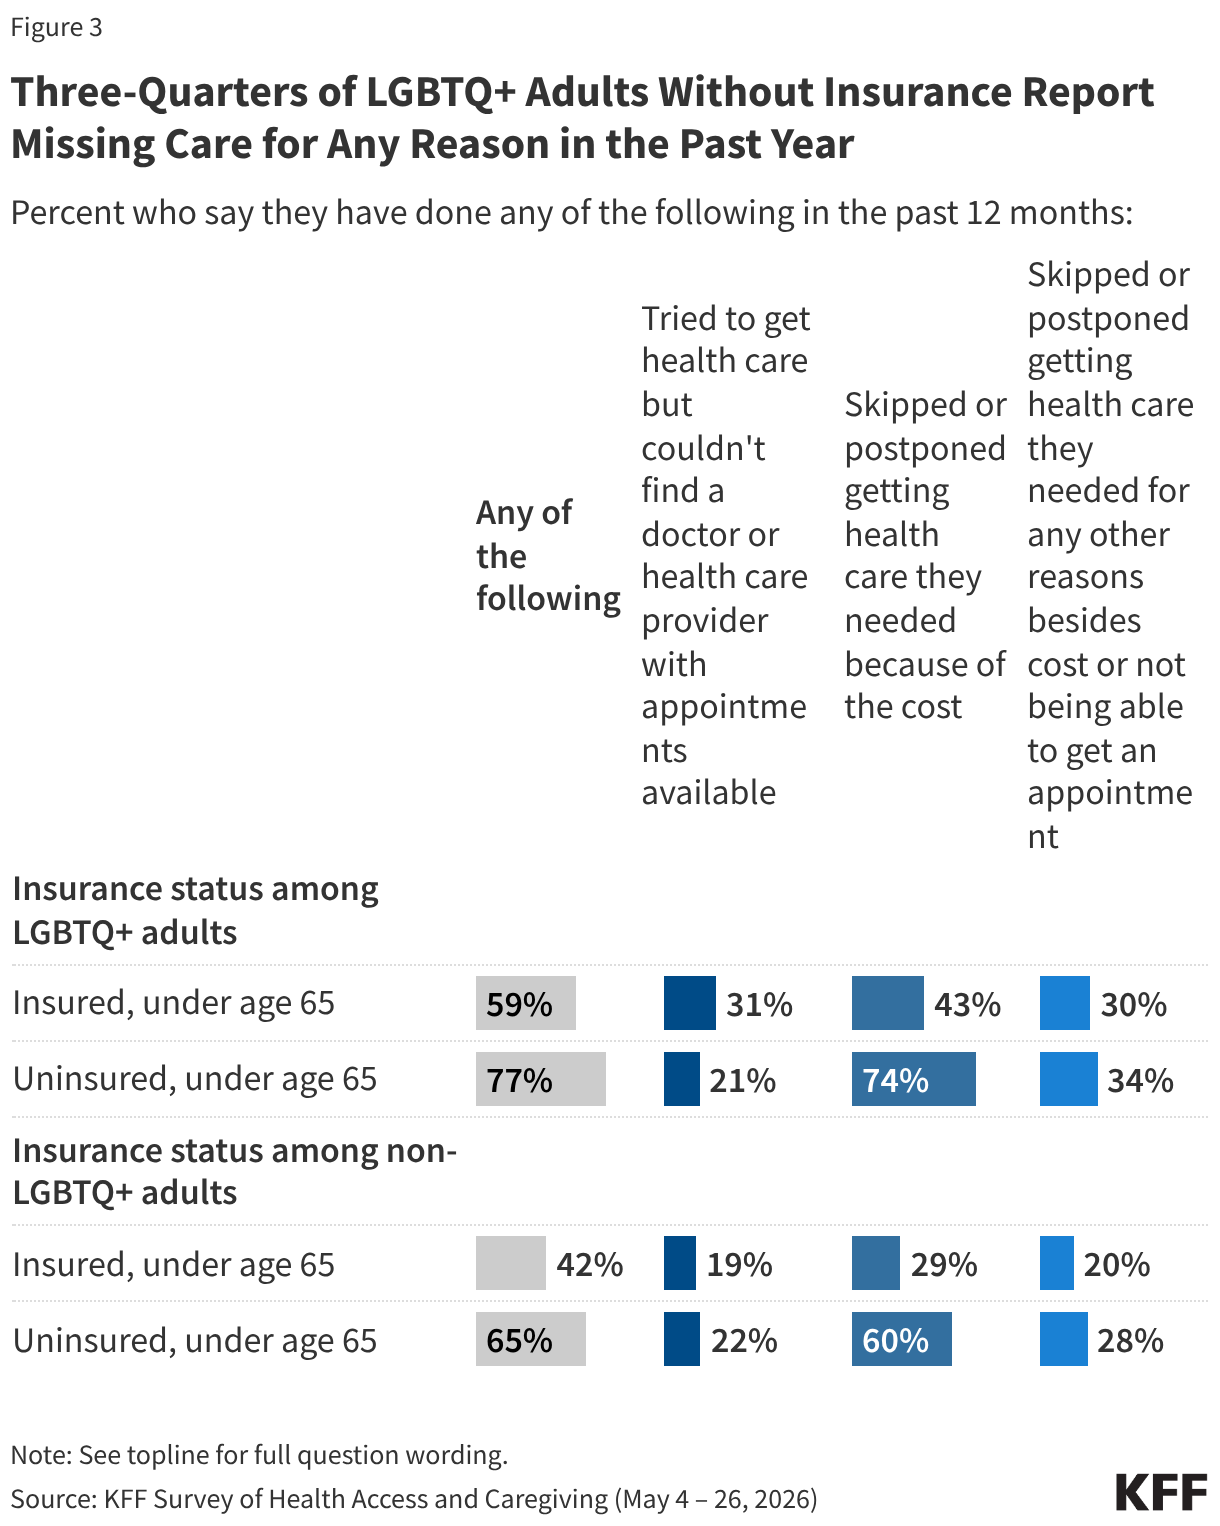
Insurance and income also play a role in accessing care. Three in four (77%) LGBTQ+ adults without health insurance report having missed or delayed care in the past year for any reason, compared to six in ten LGBTQ+ adults with health insurance. Fewer non-LGBTQ+ adults than LGBTQ+ adults without health insurance report experiencing any of the following in the past year (65% vs. 77% of uninsured LGBTQ+ adults).

Three-Quarters of LGBTQ+ Adults Without Insurance Report Missing Care for Any Reason in the Past Year (Split Bars)

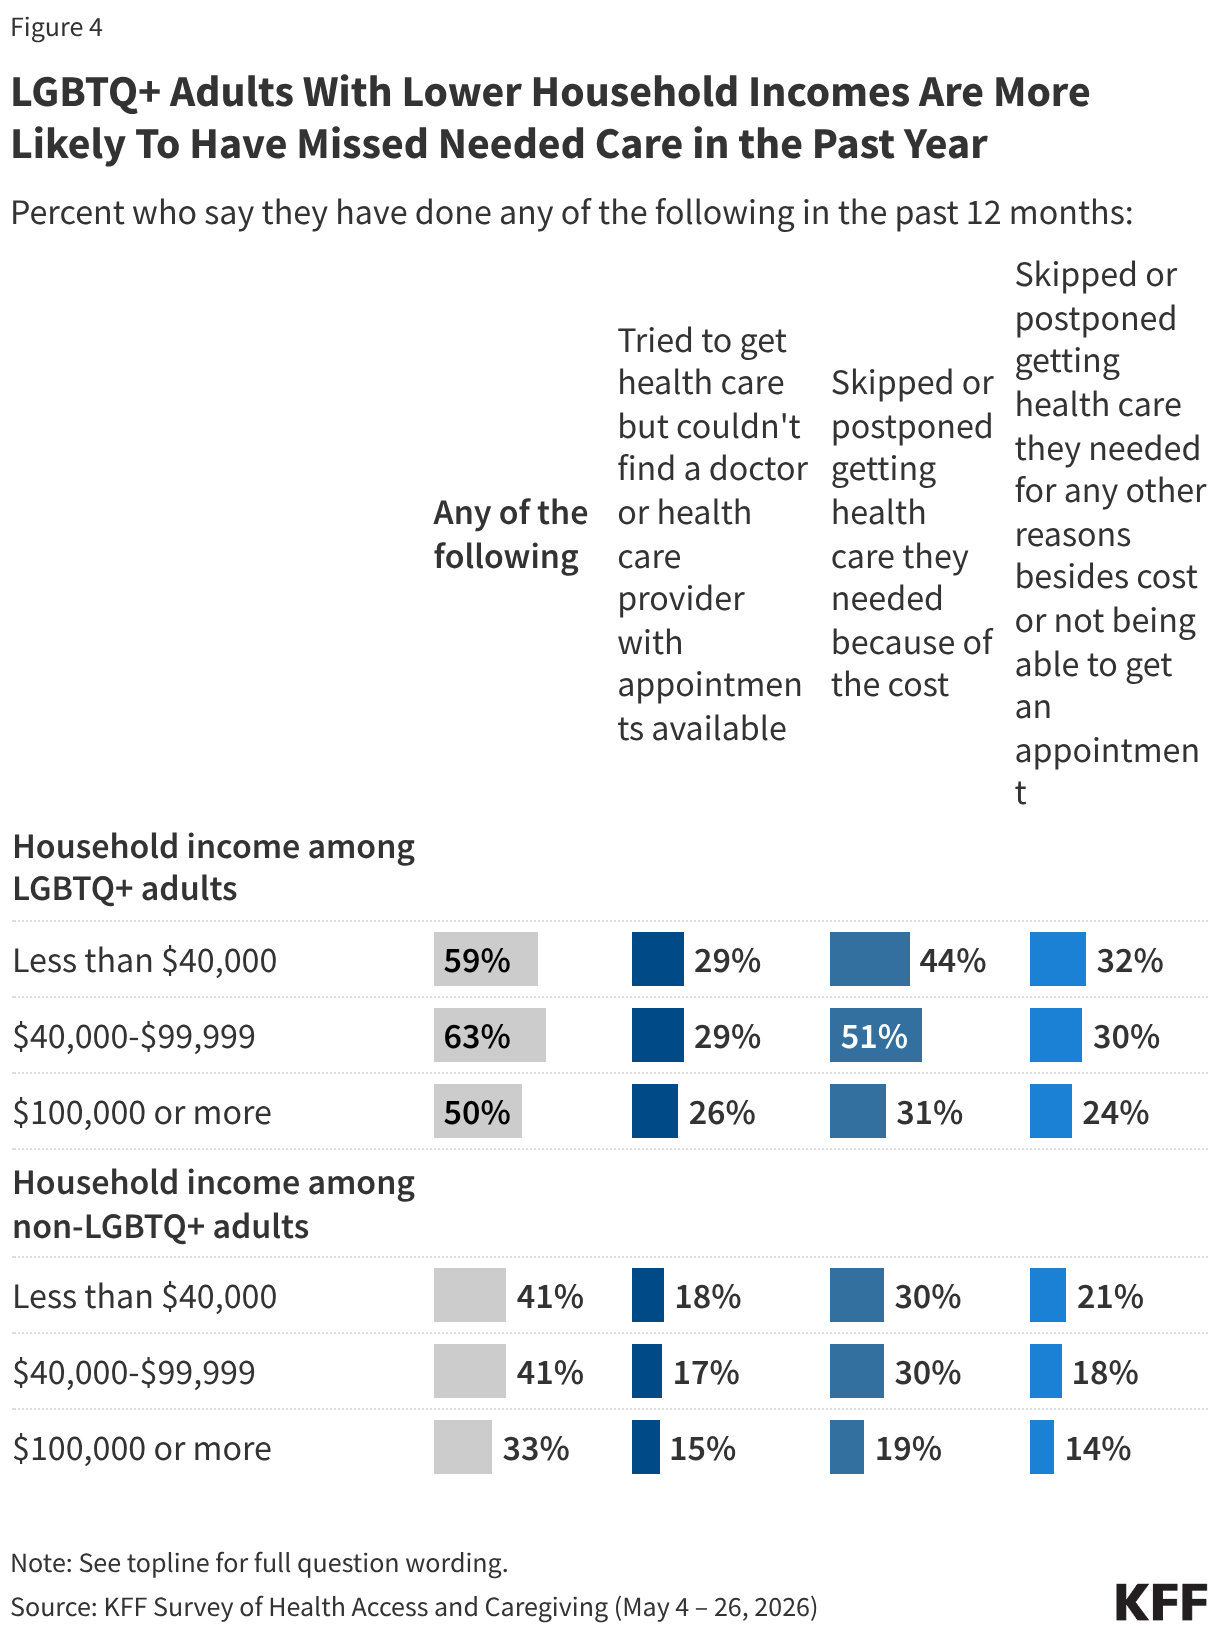
Similarly, about six in ten LGBTQ+ adults with household incomes under $40,000 a year (59%) or between $40,000 and $99,999 a year (63%) say they skipped or postponed needed care, compared to half of those with annual incomes of $100,000 or more. Even among the highest income groups or those with health insurance, LGBTQ+ adults are more likely than non-LGBTQ+ adults to say they skipped or delayed needed care in the past year.

LGBTQ+ Adults With Lower Household Incomes Are More Likely To Have Missed Needed Care in the Past Year (Split Bars)

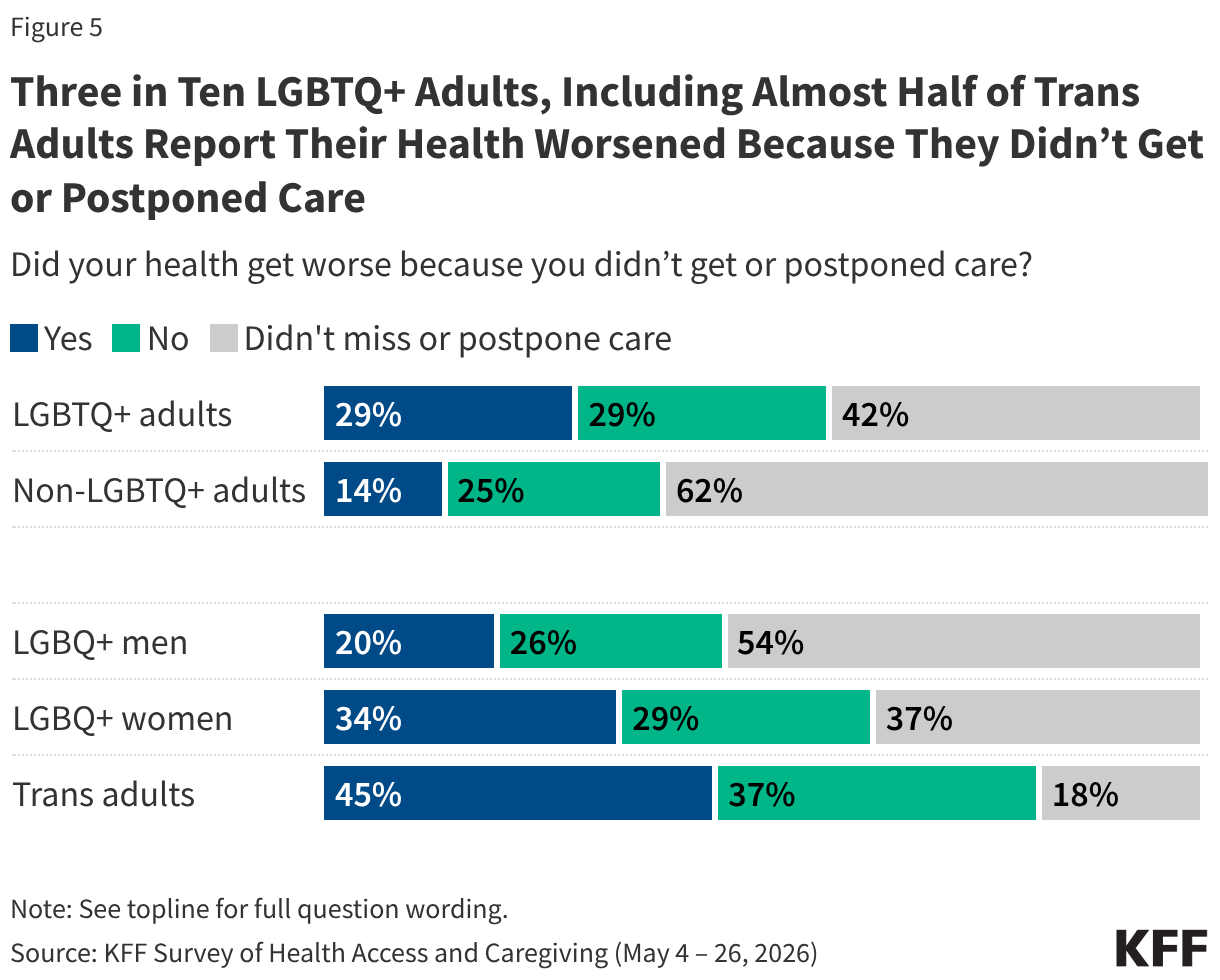
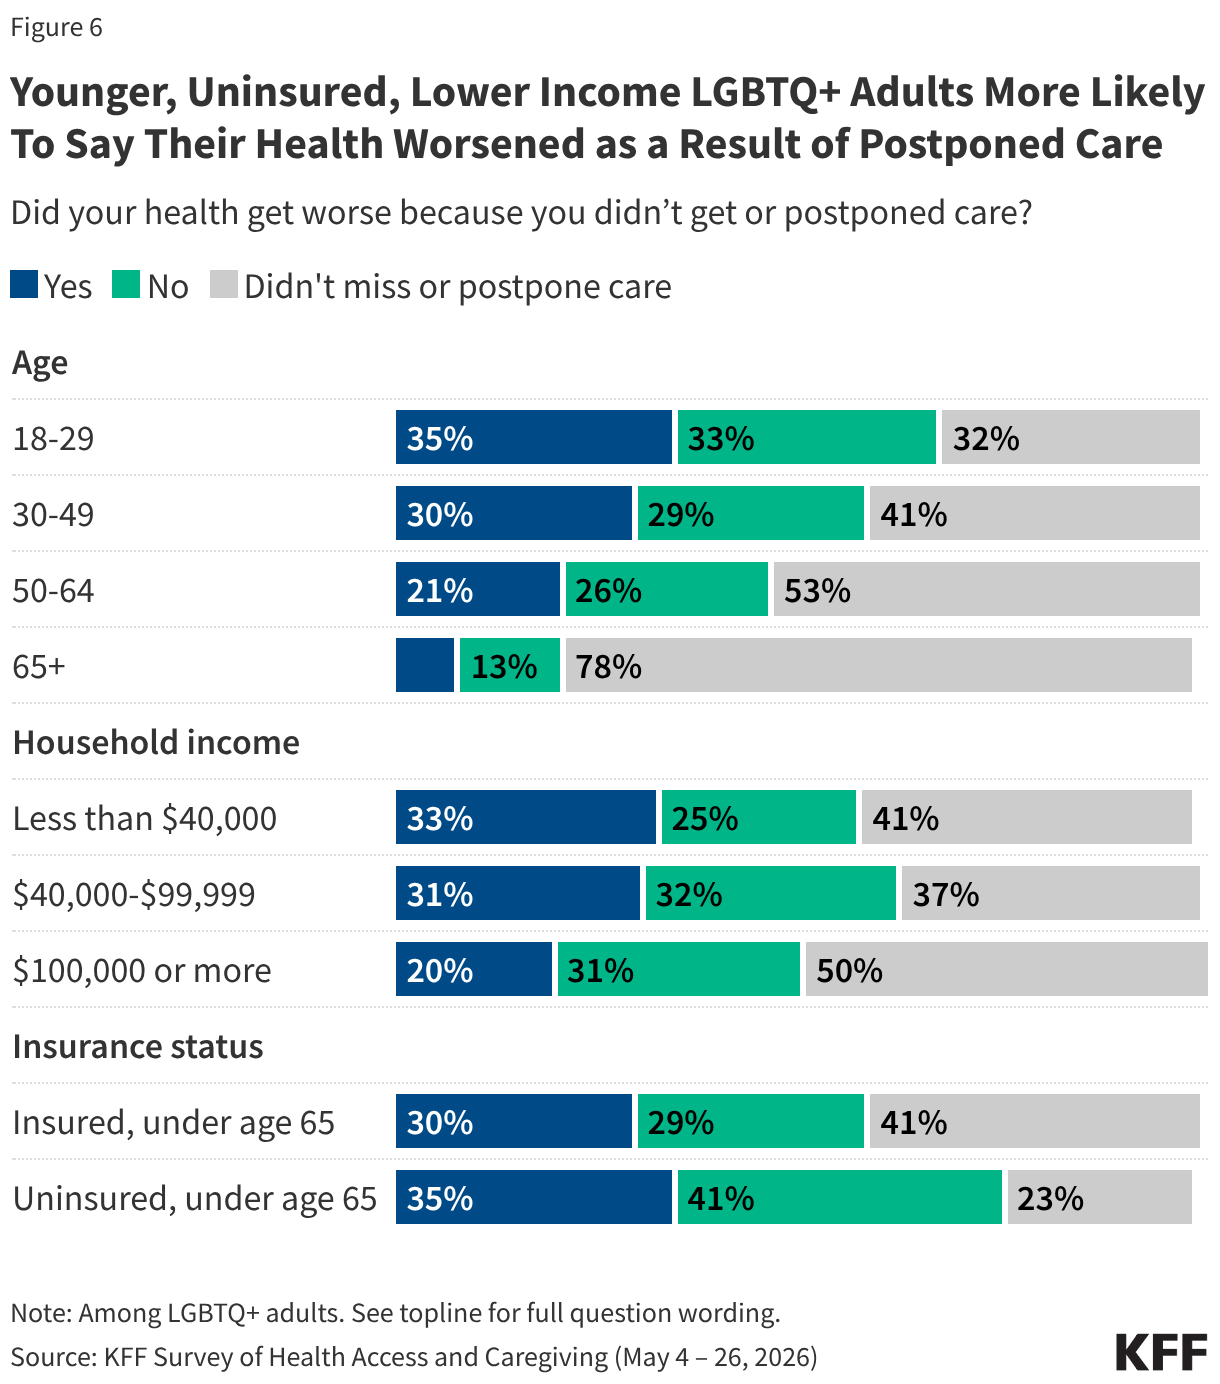
Substantial shares of LGBTQ+ adults report postponing their care worsened their health, and that number is especially pronounced among trans adults. Three in ten (29%) LGBTQ+ adults say their health got worse because they skipped or delayed care, which is about twice the share of non-LGBTQ+ adults who report the same (14%). This experience is more common among LGBQ+ women (34%) than LGBQ+ men (20%). Almost half (45%) of trans adults say they delayed or skipped care and their health got worse as a result.

Three in Ten LGBTQ+ Adults, Including Almost Half of Trans Adults Report Their Health Worsened Because They Didn’t Get or Postponed Care (Stacked Bars)

The share who say their health got worse due to postponing care also rises to roughly a third of uninsured LGBTQ+ adults (35%) and those under age 30 (35%). One-third (33%) of LGBTQ+ adults with household incomes of less than $40,000 report that their health got worse because of postponed care.

Younger, Uninsured, Lower Income LGBTQ+ Adults More Likely To Say Their Health Worsened as a Result of Postponed Care (Stacked Bars)

Impacts of Cost on Prescription Medications

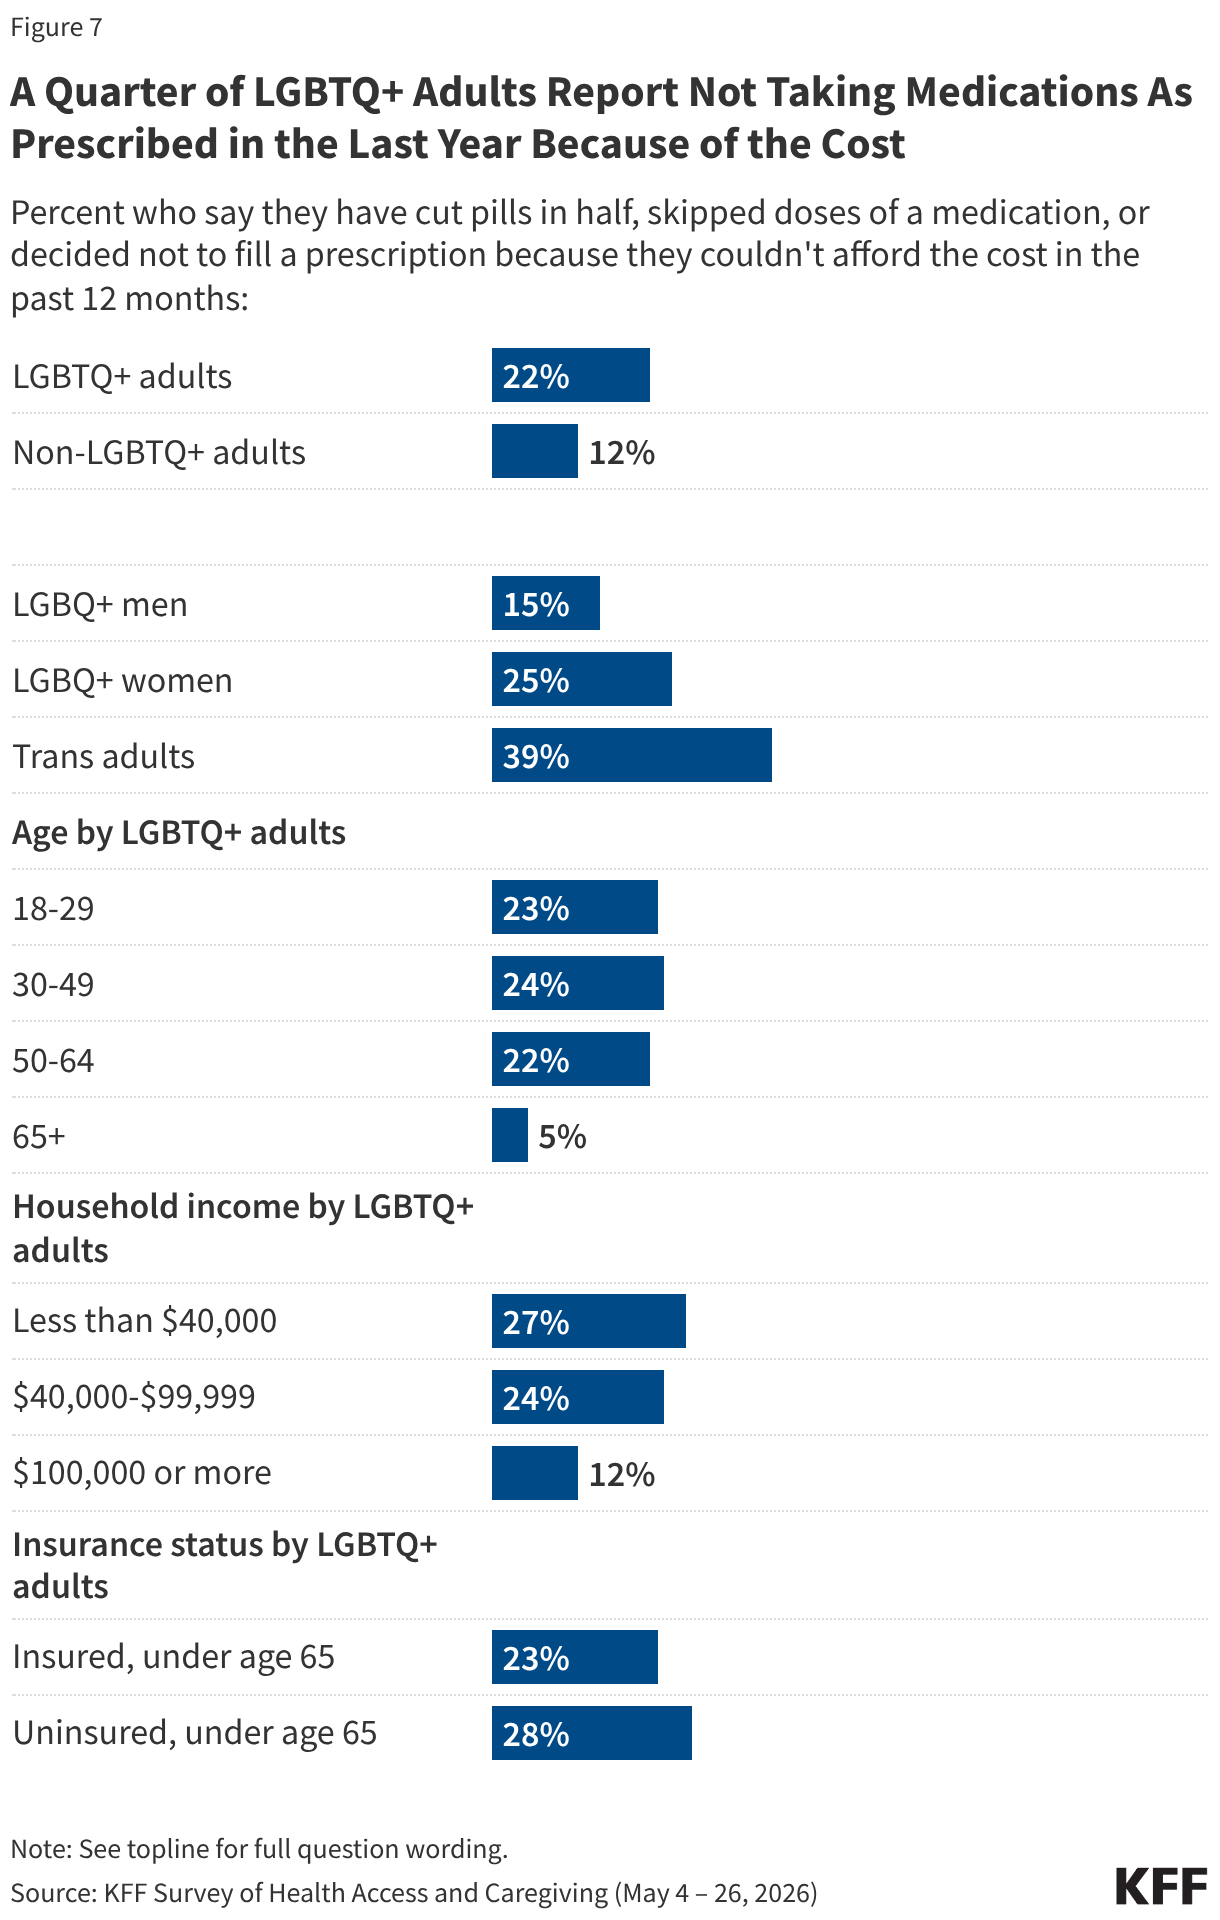
Cost barriers also affect prescription medication behavior, including among LGBTQ+ adults, with about a fifth of LGBTQ+ adults (22%) saying they’ve cut pills in half, skipped doses of a medication, or decided not to fill a prescription because they couldn’t afford the cost (compared to 12% of non-LGBTQ+ adults). Trans adults (39%), LGBTQ+ adults without insurance (28%), LGBQ+ women (25%), and younger LGBTQ+ adults (23% of those under age 30), are the most likely to report that they didn’t take their prescription medication as prescribed due to cost.

In addition, around a quarter of LGBTQ+ adults with lower incomes report cutting pills in half, skipping doses of medications, or not filling a prescription in the past year due to cost, including 27% of those with a household income of less than $40,000 a year, and 24% of those with incomes between $40,000 and $99,999 a year, compared to around one in ten (12%) of LGBTQ+ adults with incomes of $100,000 or more a year.

A Quarter of LGBTQ+ Adults Report Not Taking Medications As Prescribed in the Last Year Because of the Cost (Split Bars)

Difficulty Paying Medical Bills

Substantial shares of LGBTQ+ adults also report struggling with medical bills. Three in ten LGBTQ+ adults say they have had problems paying for or were unable to pay a medical bill, including bills for doctors, tests or labs, or medication in the past 12 months, higher than the 21% of non-LGBTQ+ adults who say the same. This includes four in ten (42%) trans adults, over a third (36%) of LGBQ+ women and two in ten (21%) LGBQ+ men.

Problems with bills can lead to important financial consequences for many LGBTQ+ adults. Two in ten (19%) LGBTQ+ adults, including two in ten (22%) LGBQ+ women and roughly one in ten (13%) LGBQ+ men say they’ve had to cut back on household expenses like food, clothing, or other basic household items in order to pay for health care costs. This experience is more common among trans adults, over one quarter of whom (28%) report the same. Overall, LGBTQ+ adults report they have cut back on necessities to pay for health care costs more commonly than non-LGBTQ+ adults (13%).
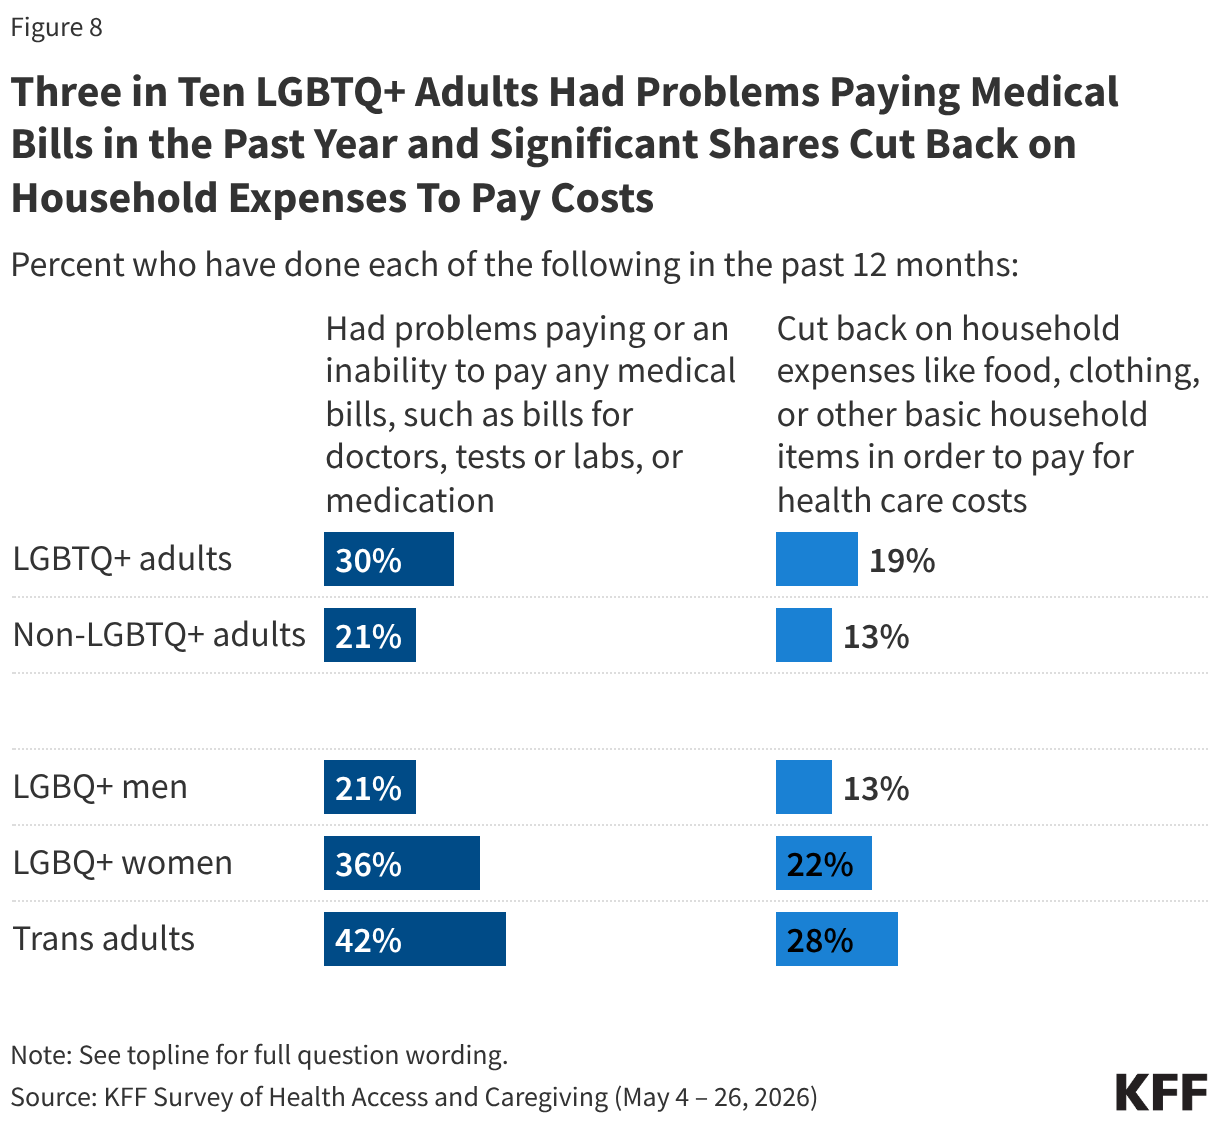
Three in Ten LGBTQ+ Adults Had Problems Paying Medical Bills in the Past Year and Significant Shares Cut Back on Household Expenses To Pay Costs (Split Bars)

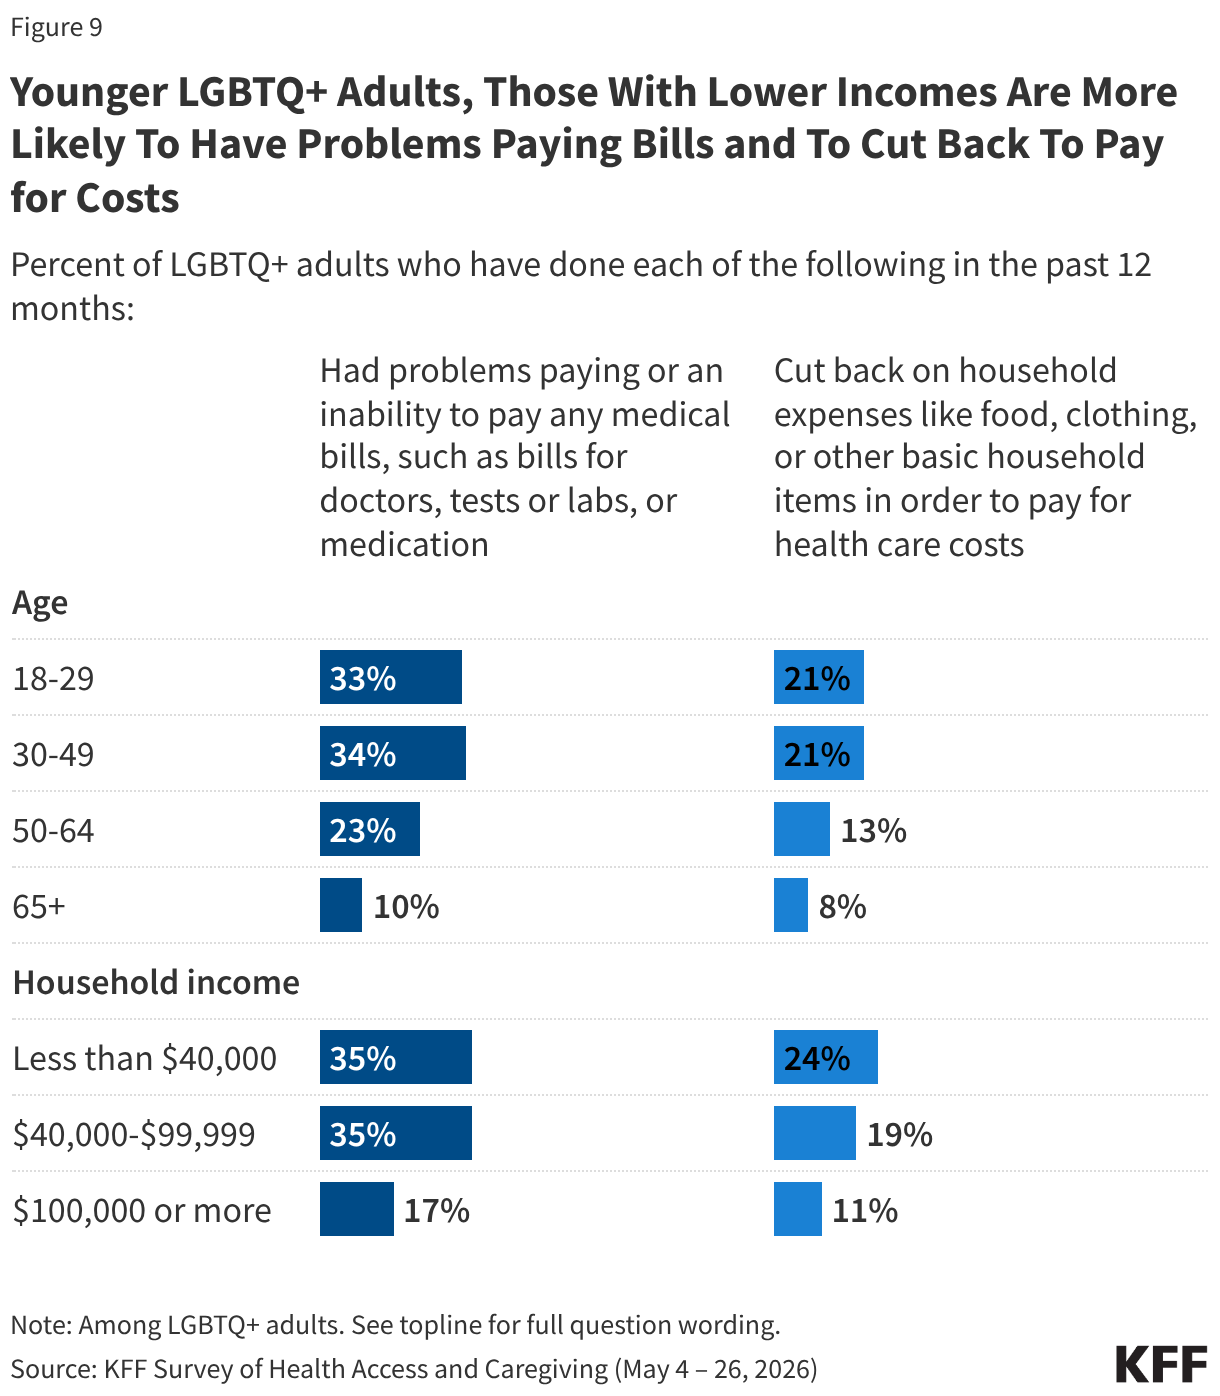
Younger LGBTQ+ adults and those with lower household incomes, two groups with considerable overlap, are among the most likely to report problems paying medical bills in the past year, with around a third of those under age 30 (33%), between 30 and 49 (34%), those with incomes of less than $40,000 a year (35%) or between $40,000 and $99,999 (35%) reporting they had problems paying or an inability to pay for any medical bills in the past year. Individuals earning over $100,000 annually and those 65 and older, who are largely covered by Medicare, are less likely to report such problems.

Younger LGBTQ+ adults and those with lower incomes are also more likely to report cutting back on expenses because of their problems paying medical bills. Overall, a quarter (24%) of LGBTQ+ adults with household incomes less than $40,000 a year say they have cut back on household expenses like food, clothing or other basic household items to pay for health care costs, compared to two in ten (19%) LGBTQ+ adults with incomes between $40,000 and $99,999 and one in ten (11%) of those with incomes of $100,000 or more a year.

Younger LGBTQ+ adults are also more likely to report cutting back on expenses because of trouble paying medical bills, including two in ten LGBTQ+ adults under age 30 and between ages 30 to 49 (21% for each) compared to one in ten (13%) LGBTQ+ adults ages 50 to 64 and one in twelve (8%) of those ages 65 and older.

Younger LGBTQ+ Adults, Those With Lower Incomes Are More Likely To Have Problems Paying Bills and To Cut Back To Pay for Costs (Split Bars)

Insurance Delays or Denials

Treatments or medications recommended by a provider may be delayed, and in some cases, an insurance company may deny coverage for the recommended medication or treatment after or during the care process. While insurance coverage helps some LGBTQ+ adults deal with access and cost issues, many face other challenges such as delayed or denied care.

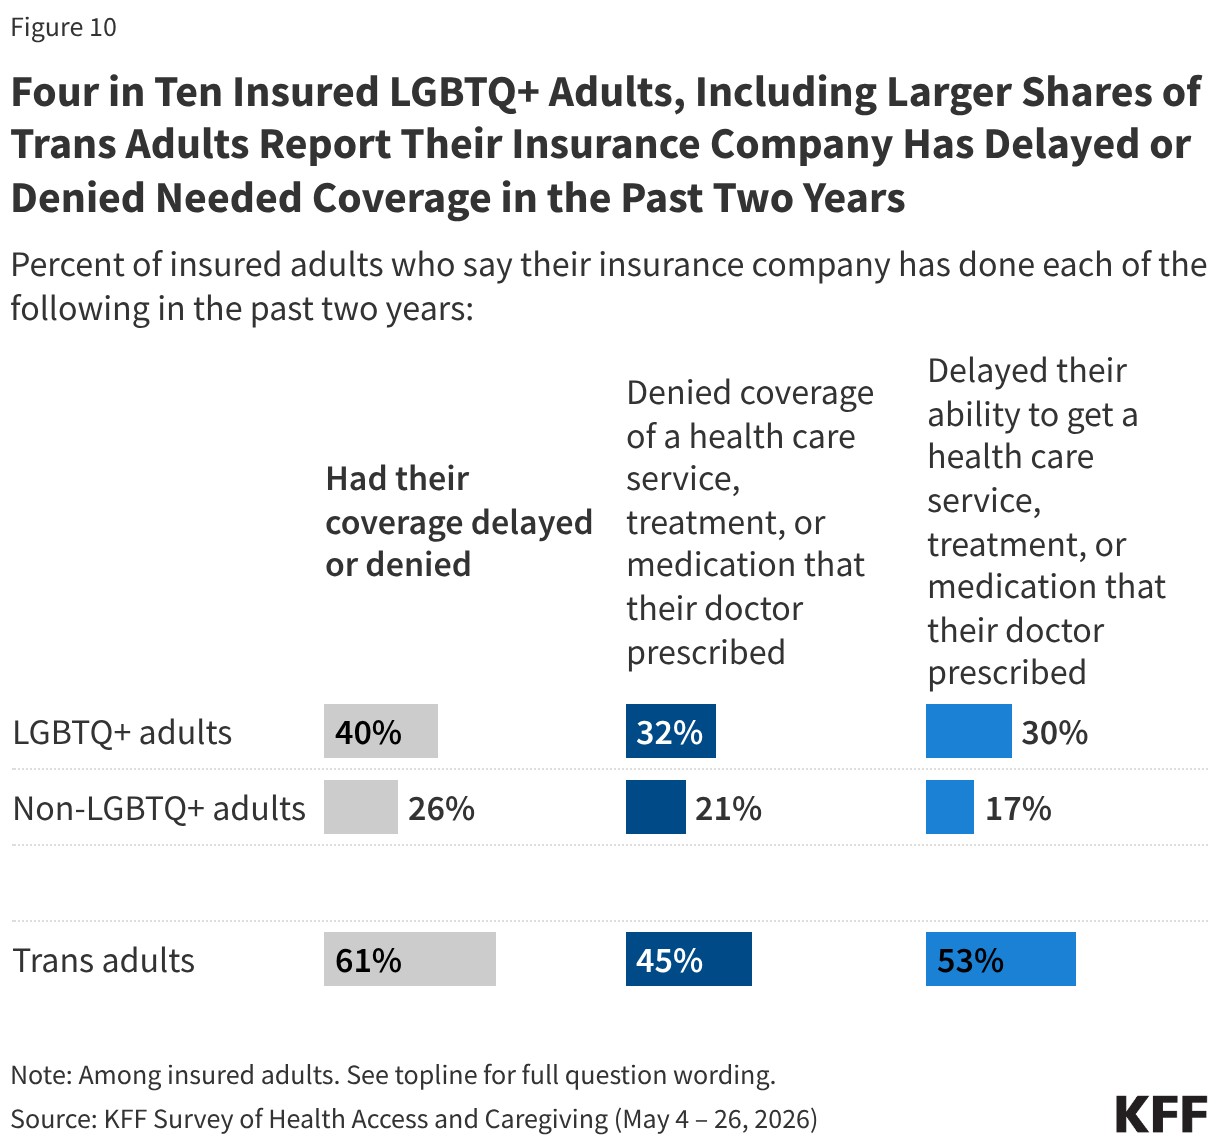
Roughly one-third of insured LGBTQ+ adults say their insurance company denied coverage (32%) or delayed (30%) their ability to get a health care service, treatment, or medication that their doctor prescribed in the past two years. Four in ten say coverage has either been delayed or denied. These shares are substantially higher than among non-LGBTQ+ adults, about a quarter (26%) of whom say they’ve experienced a denial of service (21%) or delay (17%) in the past two years.

These experiences are particularly common among trans adults, roughly six in ten (61%) of whom say they’ve been delayed (53%) or denied (45%) coverage by their insurance for a service, treatment, or medication prescribed by their doctor in the past two years.

Four in Ten Insured LGBTQ+ Adults, Including Larger Shares of Trans Adults Report Their Insurance Company Has Delayed or Denied Needed Coverage in the Past Two Years (Split Bars)

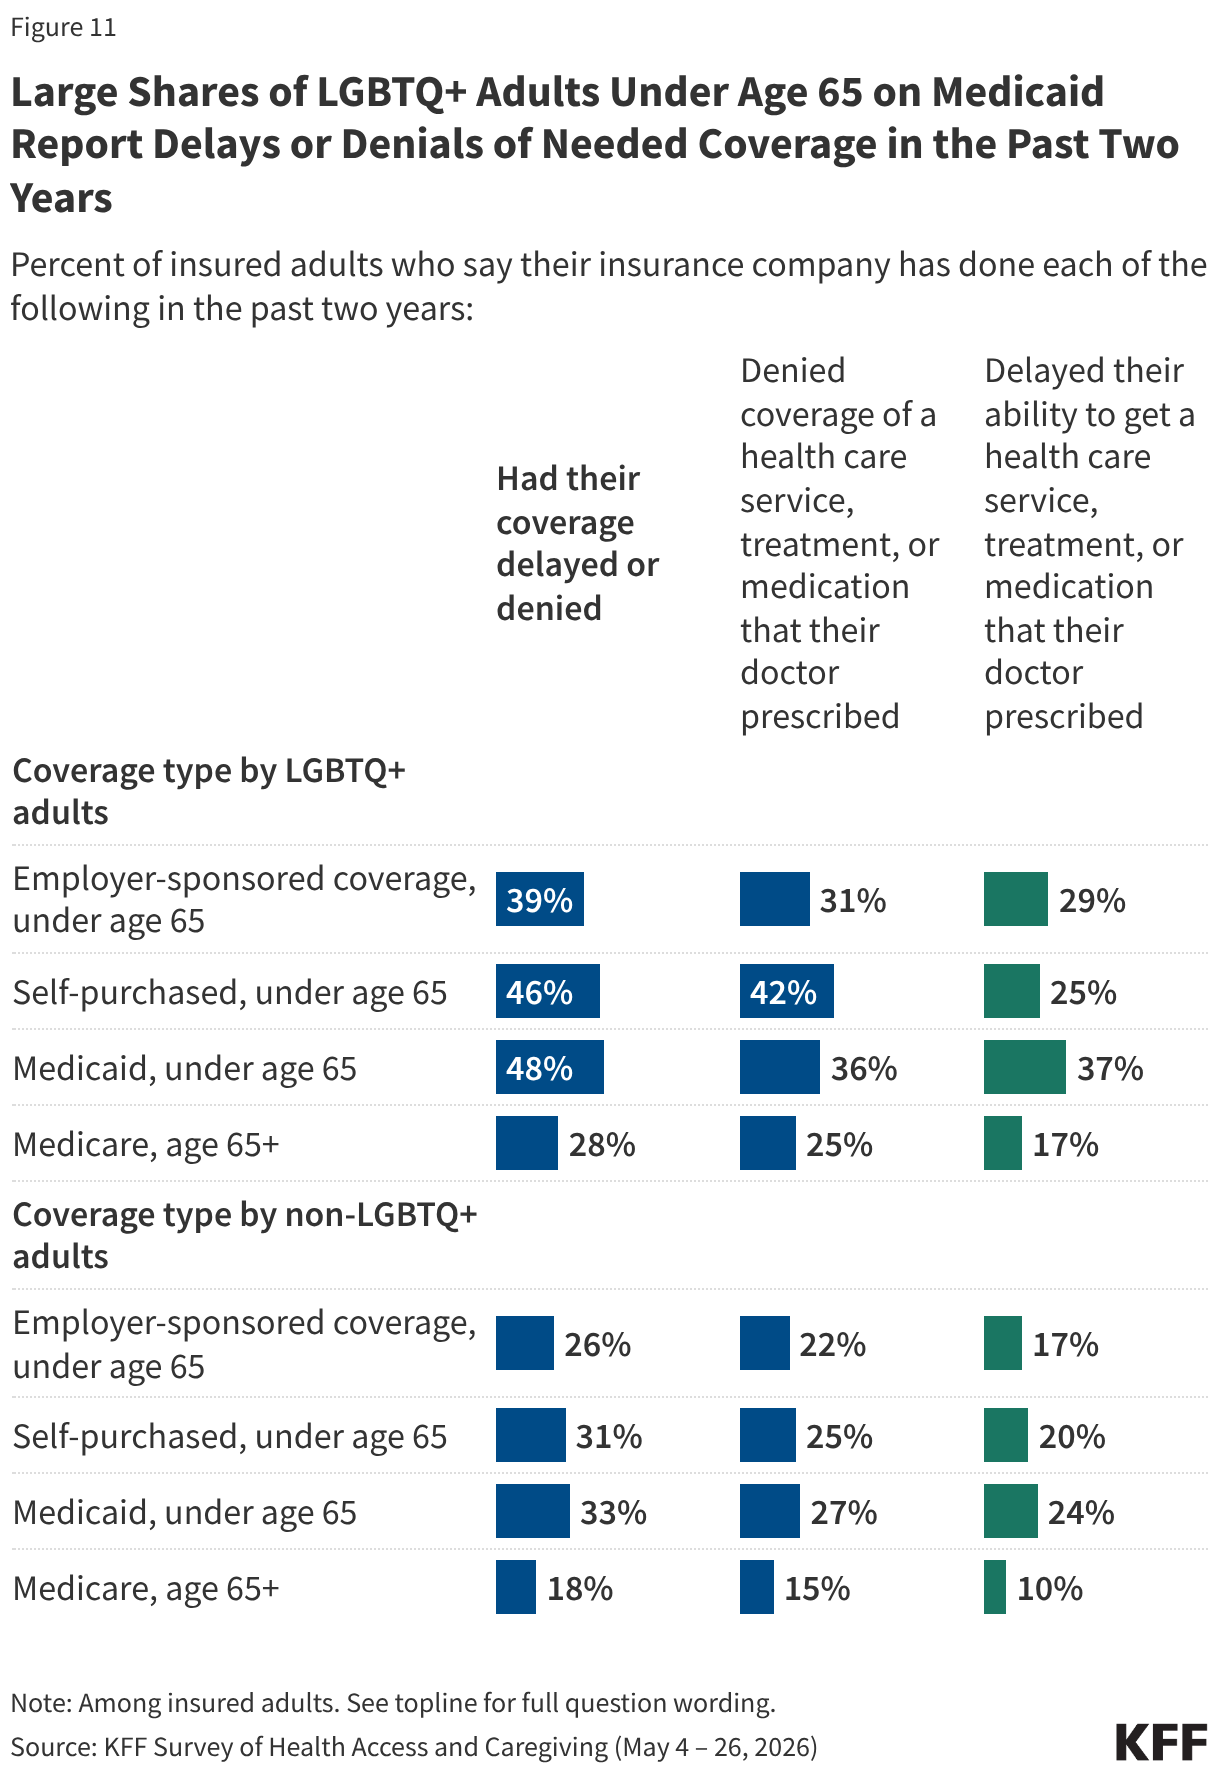
Delays and denials of coverage for LGBTQ+ adults vary based on what type of insurance they have. Individuals with either self-purchased plans or Medicaid report experiencing these most often. Roughly half (48%) of LGBTQ+ adults under age 65 who have Medicaid (48%) or self-purchased insurance (46%) say their insurance company has denied or delayed health care services, treatments, or medications in the past two years. Given that Medicaid plays a larger role in covering LGBTQ+ people, this coverage difference may in partially explain some of the disparate challenges this group faces with delays and denials.  

Roughly four in ten (39%) LGBTQ+ adults under age 65 with employer-sponsored insurance say the same while just three in ten (28%) LGBTQ+ adults ages 65 and older with Medicare report experiencing recent delays and denials.

The share of LGBTQ+ adults with various types of health insurance who report delays or denials of needed care is larger than the share of non-LGBTQ+ adults who say the same. Roughly a third of those non-LGBTQ+ adults with Medicaid (33%) or self-purchased insurance (31%), around a quarter (26%) of those with employer-sponsored coverage, and around two in ten (18%) of non-LGBTQ+ adults who have Medicare and are ages 65 or older report these issues.
Large Shares of LGBTQ+ Adults Under Age 65 on Medicaid Report Delays or Denials of Needed Coverage in the Past Two Years (Split Bars)

The KFF Survey of Health Status and Caregiving was a series of questions designed and implemented by KFF with the SSRS Opinion Panel Mega-Omnibus. The survey was conducted May 4 – May 26, 2026, online and by telephone among a nationally representative sample of 25,873 U.S. adults in English (n=25,422) and in Spanish (n=451).

The SSRS Opinion Panel is a nationally representative probability-based panel where panel members are recruited randomly in one of two ways: (a) Through invitations mailed to respondents randomly sampled from an Address-Based Sample (ABS) through the U.S. Postal Service’s Computerized Delivery Sequence (CDS); (b) recruited via random digit dial (RDD) telephone sample of cell phone numbers connected to a prepaid cell phone. Both samples were provided by Marketing Systems Group (MSG). The combined sample was reached either online (n=24,875) or over the phone (n=998) based on the panelist’s stated preference. For the online panel component, invitations were sent to panel members by email followed by up to four reminder emails and up to two reminder text messages (if consented to receive SMS).

The questions designed by KFF were included as part of a multi-stakeholder effort designed to survey all individuals currently empaneled in the SSRS Opinion Panel, with each organization paying for and having independent editorial control over its survey questions.  Substantive questions from other outside stakeholders are redacted in this report. The SSRS survey team designed the questionnaire in order to minimize potential bias from question ordering. For more information, please contact SSRS.

Respondents who completed on the web received a $5 electronic gift card incentive (some harder-to-reach groups received a $10 electronic gift card). Respondents who completed the survey on the phone received $10 via a physical check in the mail. In order to ensure data quality, cases were removed if they failed two or more quality checks: (1) attention check questions in the online version of the questionnaire, (2) had over 10% item non-response, or (3) had a length of less than 30% of the mean length by mode. Based on this criterion, 69 cases were removed.

Data were weighted to represent adults 18+ in the United States. The Panel-wide base weight adjusts for the SSRS Opinion Panel recruitment and retention process. Because all current panelists (except 2026 recruits) were invited to participate and no further sampling was performed, no further adjustments to the Panel-wide base weight were necessary before applying it to the survey data.

With the Panel-wide base weight applied, the survey-data were weighted to match the sample’s demographic profile to the same target population parameters used in the calibration of the entire SSRS Opinion Panel. The demographic variables included in weighting for the general population sample are gender, age, race/ethnicity, and education (including interactions between these categories), as well as region, civic engagement, density, frequency of internet use, voter registration, political party identification, religion, household makeup, and home ownership. Final calibrated weights are trimmed at the 2nd and 98th percentiles to prevent individual interviews from having too much influence.

The margin of sampling error including the design effect for the full sample is plus or minus 1 percentage points. Numbers of respondents and margins of sampling error for key subgroups are shown in the table below. For results based on other subgroups, the margin of sampling error may be higher. Sample sizes and margins of sampling error for other subgroups are available on request. Sampling error is only one of many potential sources of error and there may be other unmeasured error in this or any other public opinion poll. KFF public opinion and survey research is a charter member of the Transparency Initiative of the American Association for Public Opinion Research.

GroupN (unweighted)M.O.S.E.
Total25,873±1 percentage point
 
LGBTQ+ adults2,640± 3 percentage points
LGBQ+ men963± 5 percentage points
LGBQ+ women1,440± 4 percentage points
Trans adults185± 11 percentage points
 
Non-LGBTQ+ adults23,233± 1 percentage point


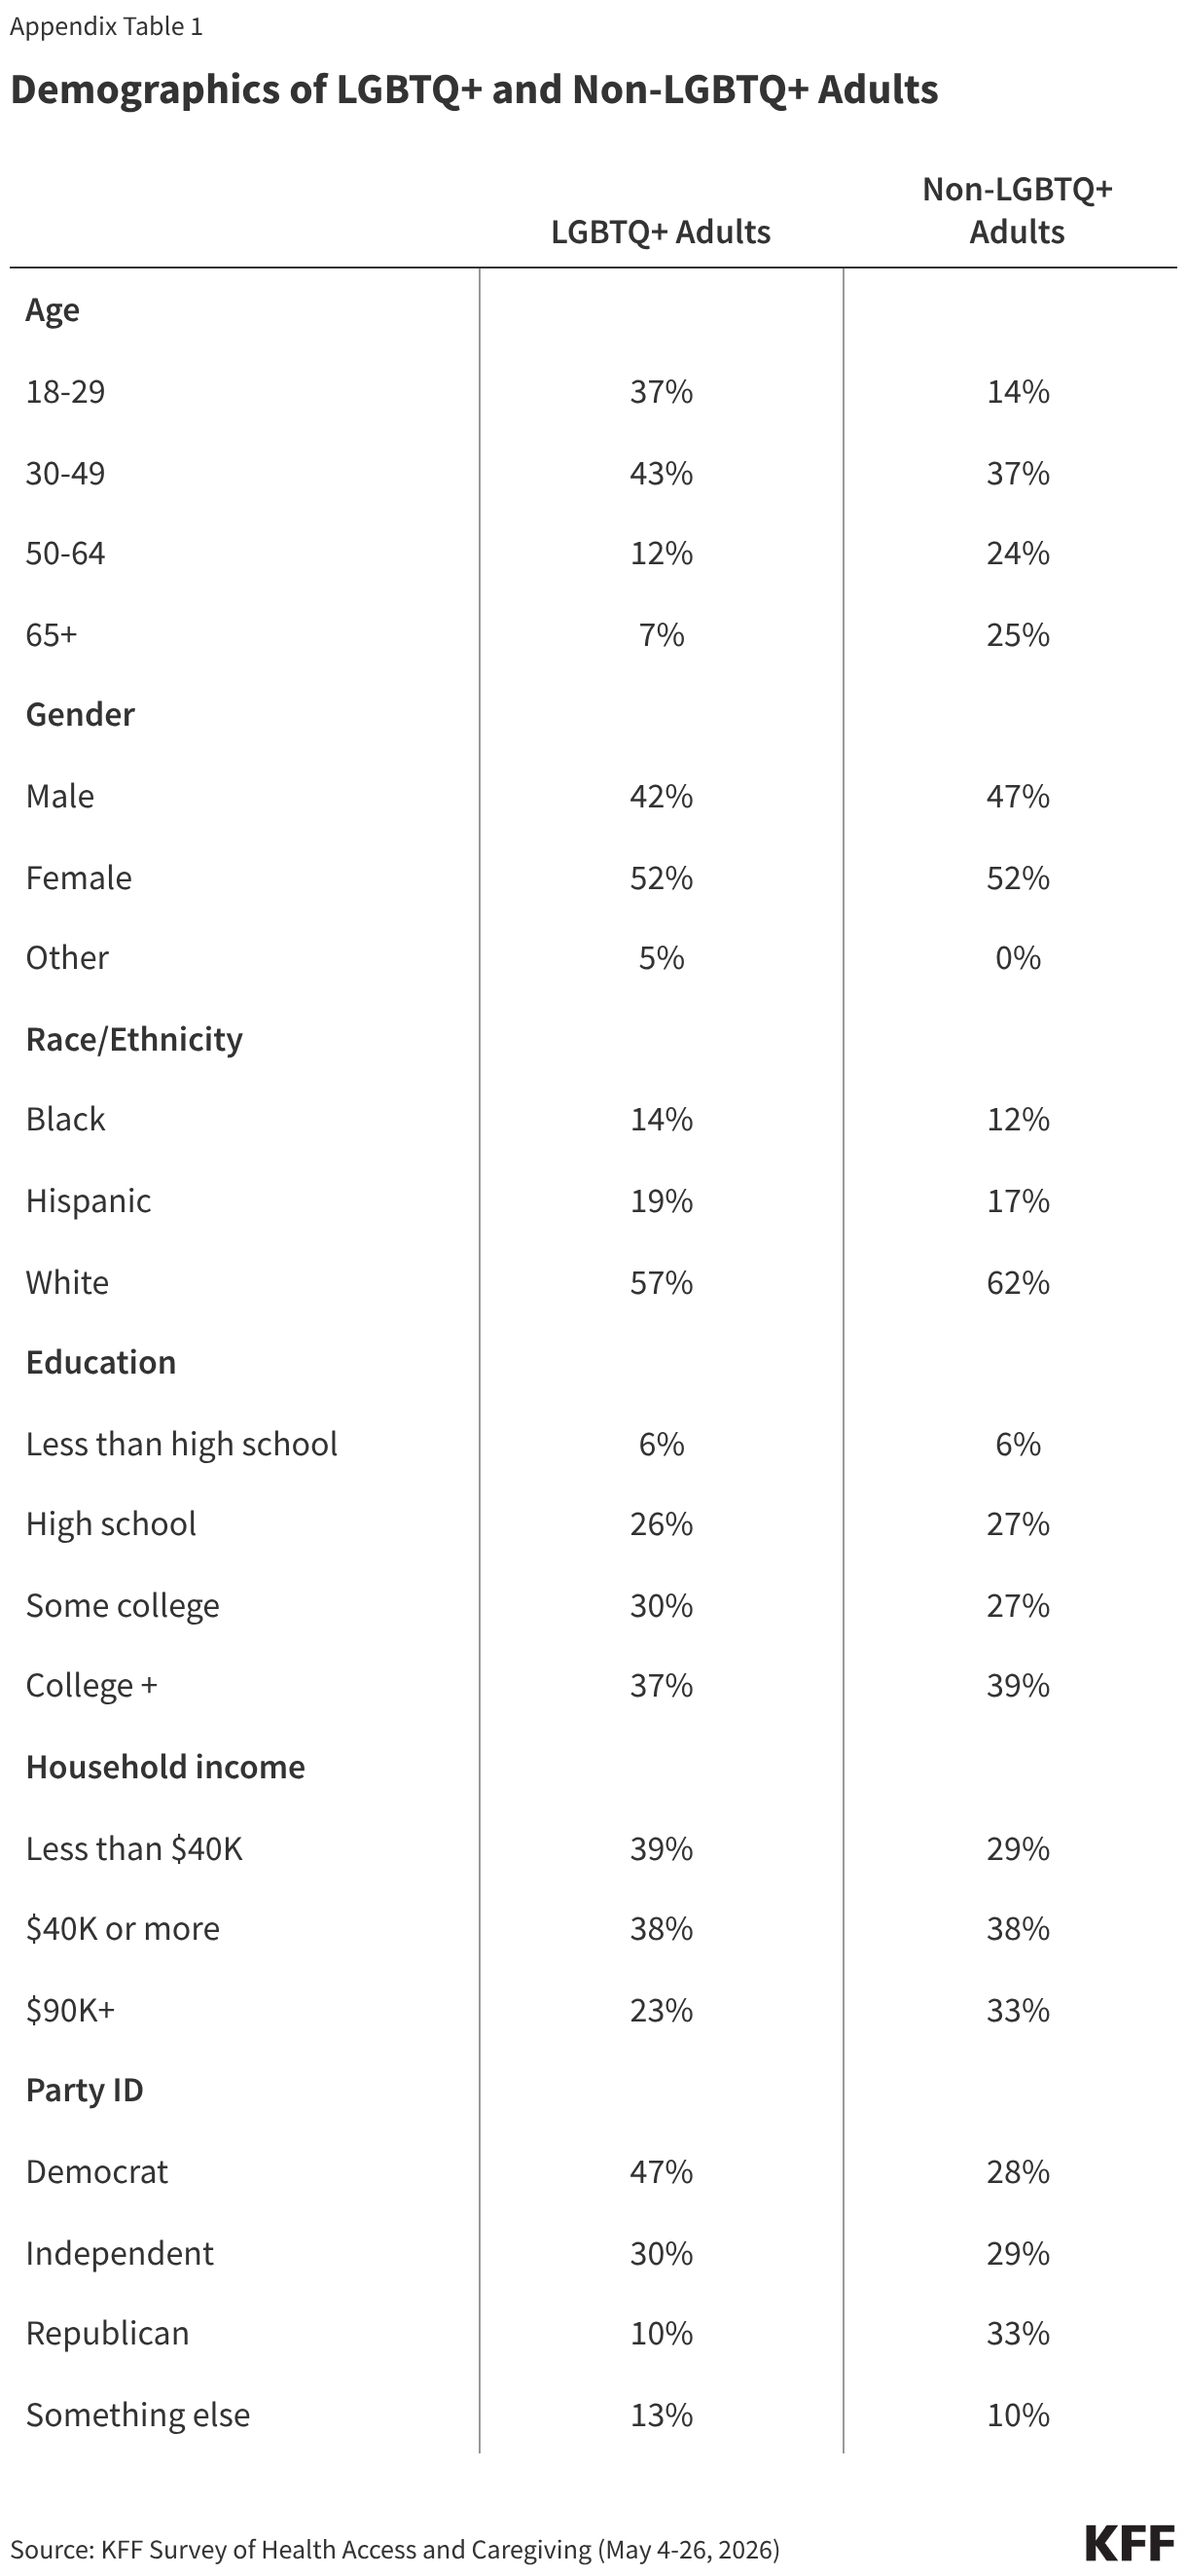
A table shows the demographics of LGBTQ+ adults vs, non-LGBTQ+ adults. LGBTQ+ adults tend to be younger. For example, 37% of LGBTQ+ adults are 18-29 years old compared to 14% of non-LGBTQ+ adults. 5% of LGBTQ+ adults say they have a gender other than male or female. LGBTQ+ adults have a similar distribution related to educational attainment and race/ethnicity compared to non-LGBTQ+ adults. LGBTQ+ adults have lower incomes and are more likely to be democrats than non-LGBTQ+ adults.

VOLUME 53

Different State Regulatory Approaches Reflect Open Questions About AI Mental Health Tools


Highlights

States are taking different regulatory approaches to AI mental health tools in response to concerns about chatbots providing inaccurate or potentially dangerous advice. Laws and pending legislation in some states restrict AI from providing or advertising itself as therapy, while others focus on data protections, disclosures, and requirements for patient consent.


AI & Emerging Technology

States Move to Regulate AI Mental Health Tools with Varying Approaches

Concerns about AI chatbots providing wrong or potentially dangerous advice have prompted legislative activity in multiple states, following documented cases of chatbots responding inappropriately to mental health-related prompts and allegations that interactions with AI were a contributing factor in multiple suicides. AI chatbots have also been documented giving false or misleading responses to health-related questions, including cases where chatbots reinforced users’ inaccurate beliefs rather than correcting them. 

As about one in six (16%) adults, including three in ten (28%) adults under 30, say they have used AI tools for mental health information or advice in the past year, states have begun to use regulations to address these concerns, with different approaches:

  • Restricting AI from providing or claiming to be mental health care. Laws in Illinois, Nevada, Tennessee, Vermont, and Rhode Island have restricted the use of AI in mental health care, either by restricting what the tools are allowed to do or how they are allowed to be advertised. Most laws in this group still allow for licensed professionals to use AI in some capacity, including laws in Colorado and Vermont that both explicitly allow administrative use of AI tools.
  • Focusing on data protection and disclosure. A law in Utah passed last year takes a different approach than banning the use of unsupervised mental health chatbots outright. Instead, the state requires data privacy protections and safety disclosures while still permitting their use. An additional law in Rhode Island also includes a version of this in addition to bans on the independent practice of therapy by AI, requiring patient consent and notification when AI is used to document clinical visits. 
  • Pending legislation largely mirrors one of these approaches. Bills still pending in both California and Pennsylvania would restrict AI from independently delivering or recommending psychotherapy services. A separate bill in Pennsylvania and another in New Jersey focus on disclosure and data protections instead.

Why This Matters: The policy approaches have varied by state, with some states enacting restrictions on AI providing or representing itself as mental health care, while others have focused more on disclosure and data practices. The differences reflect an unresolved policy question about whether AI should primarily be treated as a clinical support tool, a consumer technology, or a form of health care requiring professional oversight.


Recent Developments

Executive Order Calls for Changes to Childhood Vaccine Schedule, As Officials Repeat Unsupported Claims About Vaccine Safety

What happened?

An executive order signed earlier this month by President Trump called for further changes to the childhood vaccine schedule, including calling for the combined MMR vaccine to instead be offered as separate shots, and new research on vaccine timing. Although the EO does not explicitly mention autism, Trump repeatedly connected vaccines to rising autism rates during an event for its signing, claiming that the action would lower autism diagnoses.

What does public opinion research tell us about people’s perceptions of vaccine safety?

KFF’s June 2026 Tracking Poll on Health Information and Trust found that two-thirds of adults (66%) had heard the false claim that MMR vaccines had been proven to cause autism, with about six in ten (61%) expressing some level of uncertainty, saying the claim was either “probably true” (22%) or “probably false” (39%). That level of uncertainty has remained stable since KFF began asking about belief in that false claim in June 2023, even as research has continued to find no causal association. Notably, few adults (4%) say they think this myth is “definitely true,” while a larger share (33%) say it is “definitely false.”

Eight in ten adults (81%) in the June survey said they were very or somewhat confident in the safety of these vaccines for children, and 84% of parents said the same in the KFF/The Washington Post Survey of Parents conducted in summer 2025. 

How is this reflected in online conversations?

Claims about vaccines and autism, both perpetuating and debunking a connection, remain a prominent part of online vaccine discourse. KFF’s monitoring of social media found that on August 11, the day after the EO was signed, the number of posts, reposts, and comments that mentioned keywords relating to both vaccines and autism reached their highest volume of 2026 thus far, across X, Reddit, and YouTube. On that day, more than 38,000 posts, reposts, and comments contained keywords for both of these topics, compared to a daily average of about 5,800 this year as of August 21. While it is not possible to attribute the spike in posts directly to the EO, a share of posts mentioning both vaccines and autism also included a direct reference to the order.

While many posts sought to refute a connection between autism and vaccines, some posts with high engagement repeated false claims about the alleged connection. Some of these posts included video clips of false comments made by Health and Human Services (HHS) Secretary Robert F. Kennedy Jr., including claims that “none of the vaccines have ever been tested for autism.” Another claimed that Kennedy had “debunked” existing studies about a possible connection.

What does the research on MMR vaccine safety say?

Several studies over the last decade have found no evidence of a causal association between MMR vaccines and autism. Most recently, a retrospective cohort study of more than 2.5 million children published last month found no association between the first dose of MMR vaccination, typically given between 11.5 and 24 months, and autism diagnosis. The new study did not specifically examine the second dose, which is usually given between ages 4 and 6.

There have been no deaths linked to combined MMR vaccination in healthy people, which had been administered more than 800 million times as of 2021.

Why This Matters

Beyond directly suggesting a causal link between vaccines and autism where none has been proven, official calls for more research into a question the scientific consensus already regards as settled introduce an unwarranted perception of uncertainty. These calls may incorrectly imply that existing evidence is inconclusive or that the question remains genuinely open, a framing that research shows can undermine public trust when applied to questions that are already settled. KFF polling from May showed that among parents who reported skipping or delaying vaccines for their children, a large share expressed mixed and uncertain beliefs across several common vaccine myths, underscoring the connection between confusion, uncertainty and these parents’ behavior.


What We’re Watching

False Claims About COVID Vaccines and Miscarriage Follow Release of Fauci Texts

Claims that COVID-19 vaccines during pregnancy pose a serious risk of miscarriage resurfaced earlier this month after Republican Senators released text messages from former NIAID Director Anthony Fauci’s government cell phone. In one message, from January 2021, Fauci noted the theoretical concern that fever after a second dose of the vaccine could be associated with miscarriage. The message was sent several months before the Centers for Disease Control and Prevention (CDC) completed its analysis of vaccine safety during pregnancy. The agency did not recommend the vaccine during pregnancy until August 2021, after its analysis showed no increased risk of miscarriage.

KFF media monitoring found multiple highly engaged-with social media posts amplifying misleading claims, suggesting that concerns about miscarriage were a prominent part of the online response to the released messages. Some posts, including those shared by Senator Rand Paul, repeated the false claim that the vaccine was proven to cause miscarriage in up to 82% of pregnancies, a claim that relies on a misreading of a 2021 study whose actual finding of a 12.6% miscarriage rate was in line with prevalence generally.

Research does not support an elevated risk of miscarriage following COVID-19 vaccination. On the other hand, COVID infection during pregnancy has been shown to be associated with higher risk of both severe illness and pregnancy loss. Major medical organizations, including the American College of Gynecologists and Obstetricians (ACOG), continue to recommend vaccination during pregnancy because of the vaccines’ known safety and benefits to both the pregnant person and for infants who are too young to get vaccinated.

Why This Matters: False claims can recur in public discourse even after being debunked repeatedly over the course of several years. The claim of an 82% miscarriage rate has circulated since 2021 and been repeatedly corrected, but a fresh news hook, like the release of Fauci’s text messages, can reintroduce it to audiences who are already uncertain. A May 2022 KFF poll found that about six in ten (58%) women who were pregnant or trying to become pregnant were not confident in the vaccines’ safety during pregnancy. Widespread uncertainty has continued as official federal guidance has shifted and false claims about these vaccines’ safety have been repeated.

State Attorneys General Investigate Alleged Financial Motivations for Vaccine Recommendations

Recent investigations announced by attorneys general across multiple states are examining whether financial interests may have influenced vaccine recommendations, potentially reinforcing public skepticism about the motives of public health officials and medical organizations.

In August, Florida, Louisiana and West Virginia announced an investigation into former NIAID Director Anthony Fauci, citing journal entries released by Senator Rand Paul that detailed his communications during the pandemic. The investigation will examine Fauci’s financial awards, professional opportunities, and communications related to COVID-19 vaccines. Florida Attorney General James Uthmeier said that his state will also examine whether Fauci personally benefited from guidance he issued during the pandemic. Fauci has not been charged with a crime. The investigations follow a Senate committee voting to hold Fauci in contempt of Congress after he repeatedly invoked his Fifth Amendment right to not testify at a hearing last month.

Texas Attorney General Ken Paxton began a separate investigation into financial incentives for childhood vaccines in January, initially examining medical providers, insurers, vaccine manufacturers and other entities. It has since expanded to focus on the American Academy of Pediatrics (AAP), including whether financial relationships with pharmaceutical companies influenced its vaccine recommendations. The investigation comes as a growing number of states have moved away from following federal vaccine recommendations; as of August, most states (30, including DC) rely on non-federal sources for at least some childhood vaccine recommendations, with most following AAP guidance.

Similar claims about financial incentives have circulated for months, including from HHS Secretary Robert F. Kennedy Jr., who alleged last summer that doctors were improperly being “paid to vaccinate.” Incentive programs for providers do exist, but they are legal, not offered by vaccine manufacturers, and based on dozens of metrics beyond vaccination.

Why This Matters: Repeatedly framing vaccine recommendations as potentially driven by financial incentives could reinforce perceptions that health institutions prioritize financial interests over patient health, particularly as officials question longstanding vaccine recommendations. KFF’s April 2026 Tracking Poll on Health Information and Trust found that fewer than half of adults expressed confidence in federal health agencies like the CDC and Food and Drug Administration (FDA) to act independently without interference from outside interests.

About The Health Information and Trust Initiative: the Health Information and Trust Initiative is a KFF program aimed at tracking health misinformation in the U.S., analyzing its impact on the American people, and mobilizing media to address the problem. Our goal is to be of service to everyone working on health misinformation, strengthen efforts to counter misinformation, and build trust. 


View all KFF Monitors

The Monitor is a report from KFF’s Health Information and Trust initiative that focuses on recent developments in health information. It’s free and published twice a month.

Sign up to receive KFF Monitor
email updates


Support for the Health Information and Trust initiative is provided by the Robert Wood Johnson Foundation (RWJF). The views expressed do not necessarily reflect the views of RWJF and KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities. The data shared in the Monitor is sourced through media monitoring research conducted by KFF.

Medicaid Coverage for Women

Published: Aug 26, 2026

Medicaid, the nation’s health coverage program for people with low incomes, provides more than 39 million women across the nation with health and long-term care coverage. Women comprise the majority of the adult Medicaid population and the program offers coverage of a wide range of primary, preventive, specialty, and long-term care services that are important to women across their lifespans. Given the importance of the program for women and their families, changes to the program, such as the 2025 federal policy changes to Medicaid and the enactment of new work requirements for the Medicaid expansion population, will have significant implications for low-income women’s access to coverage and care. This data note presents key data points describing the current state of the Medicaid program as it affects women.  

Who is Eligible for Coverage?

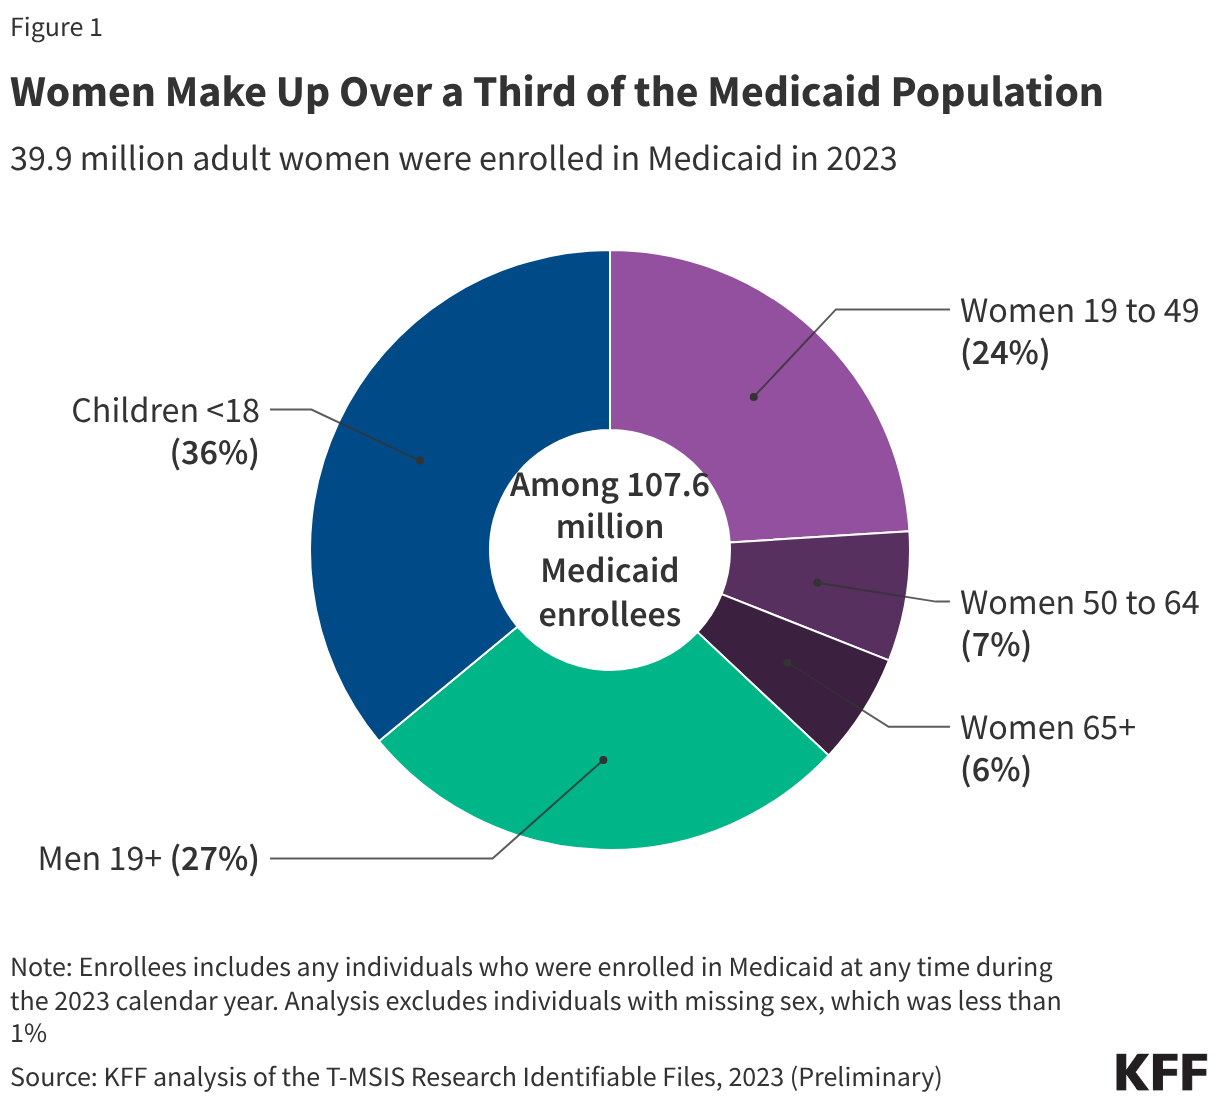
In 2023 adult women comprised 37% of the overall Medicaid population and the majority of adults on the program (Figure 1).1 Prior to the 2010 Affordable Care Act (ACA), women were more likely to qualify for Medicaid than men because of their lower incomes and because they were more likely to belong to one of Medicaid’s categories of eligibility for adults: pregnant, parent of a dependent child, senior, or person with a disability. The ACA added a new Medicaid eligibility category by extending Medicaid eligibility to nearly all adults under age 65 with incomes up to 138% of the federal poverty level (FPL), though women are still more likely than men to be covered by Medicaid.

Pie chart showing age and gender breakdown of individuals enrolled in Medicaid in 2023. Overall, adult women 19 and older make up the majority of the adult Medicaid population, and women of reproductive age (ages 19 to 49) make up 24% of the whole Medicaid population.
  • As of May 2026, 40 states and DC have opted to expand eligibility for Medicaid under the ACA, which allows women and men with low incomes below 138% FPL to qualify regardless of their pregnancy, parenting or disability status.  
  • In the 10 states that have not expanded Medicaid under the ACA, adults only qualify if they meet income criteria AND belong to one of the previously mentioned categorical eligibility groups. While there are federal eligibility minimums, states have the option to expand eligibility levels for each group up to certain limits. As a result, income eligibility criteria vary for different groups of beneficiaries within as well as between states.
  • In the states that have not adopted the ACA Medicaid expansion, approximately 576,000 women ages 19 to 64 with incomes below the federal poverty level and who are uninsured fall into a “coverage gap.” This is because they earn too much money to qualify for Medicaid in their state but not enough to qualify for assistance purchasing a private policy through their state’s ACA Marketplace, which is available for individuals with incomes between 100% FPL and 400% FPL.
  • H.R. 1, the 2025 budget reconciliation law, has made significant changes to the Medicaid program. For the first time, eligibility for adults in the ACA Medicaid Expansion group will be conditioned on meeting work requirements, starting January 1, 2027. Prior KFF research has shown that most adult women covered by Medicaid meet work requirements or could qualify for one of the law’s exemptions (including being a parent of a child under age 14), but they are at risk of losing coverage because of the administrative burdens related to reporting requirements. In 2023, approximately 40% of adult women enrolled in Medicaid were enrolled via the ACA expansion pathway.2 The Congressional Budget Office (CBO) estimates that these requirements will reduce federal Medicaid spending by $326 billion over the next 10 years but will also increase the number of uninsured by 5.3 million in 2034.

Profile of Women Under 65 Covered by Medicaid

Medicaid covers a diverse population of women who face many social, economic, and health challenges that affect their ability to receive timely and high-quality health care.  

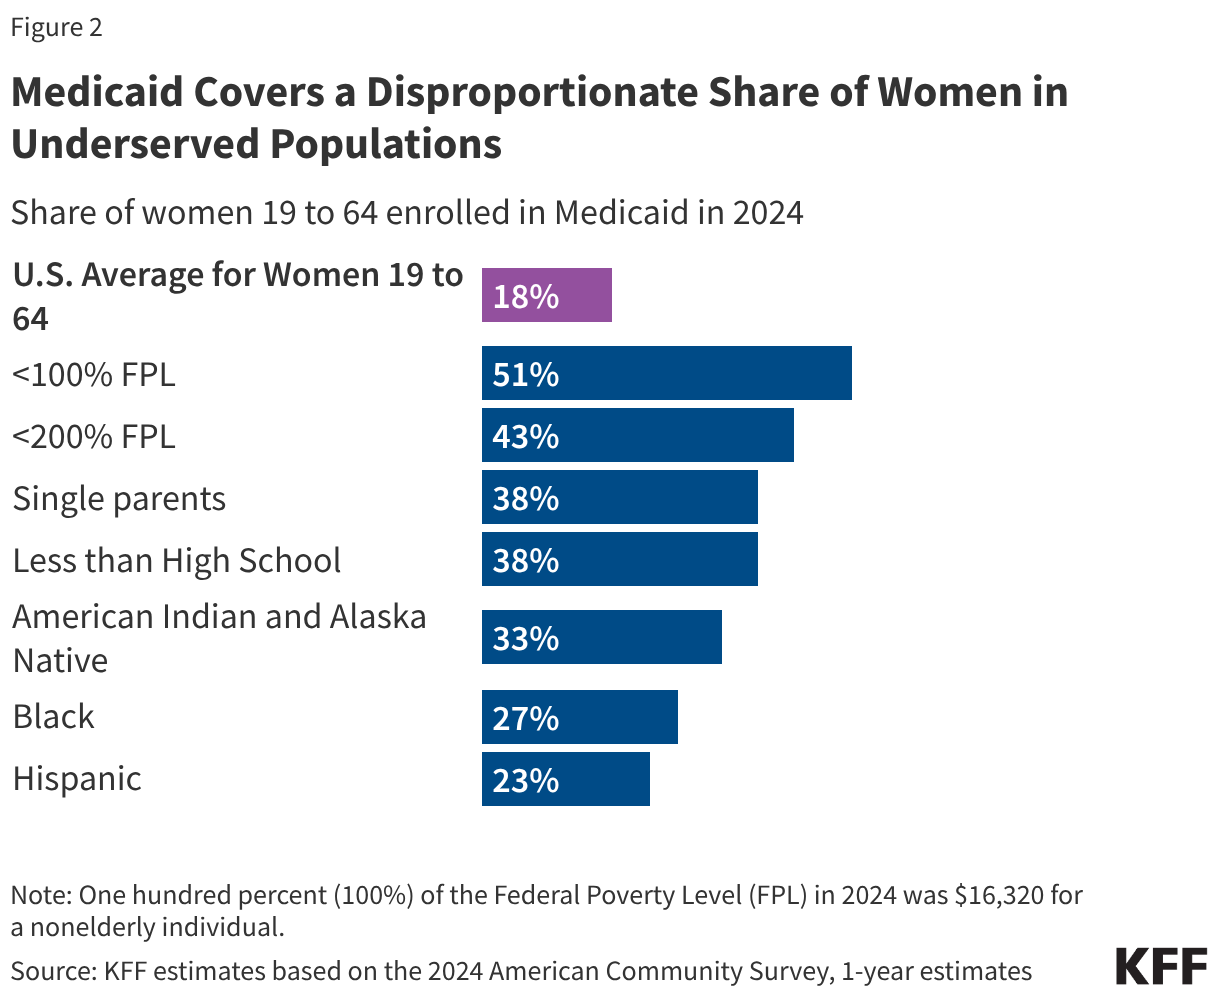
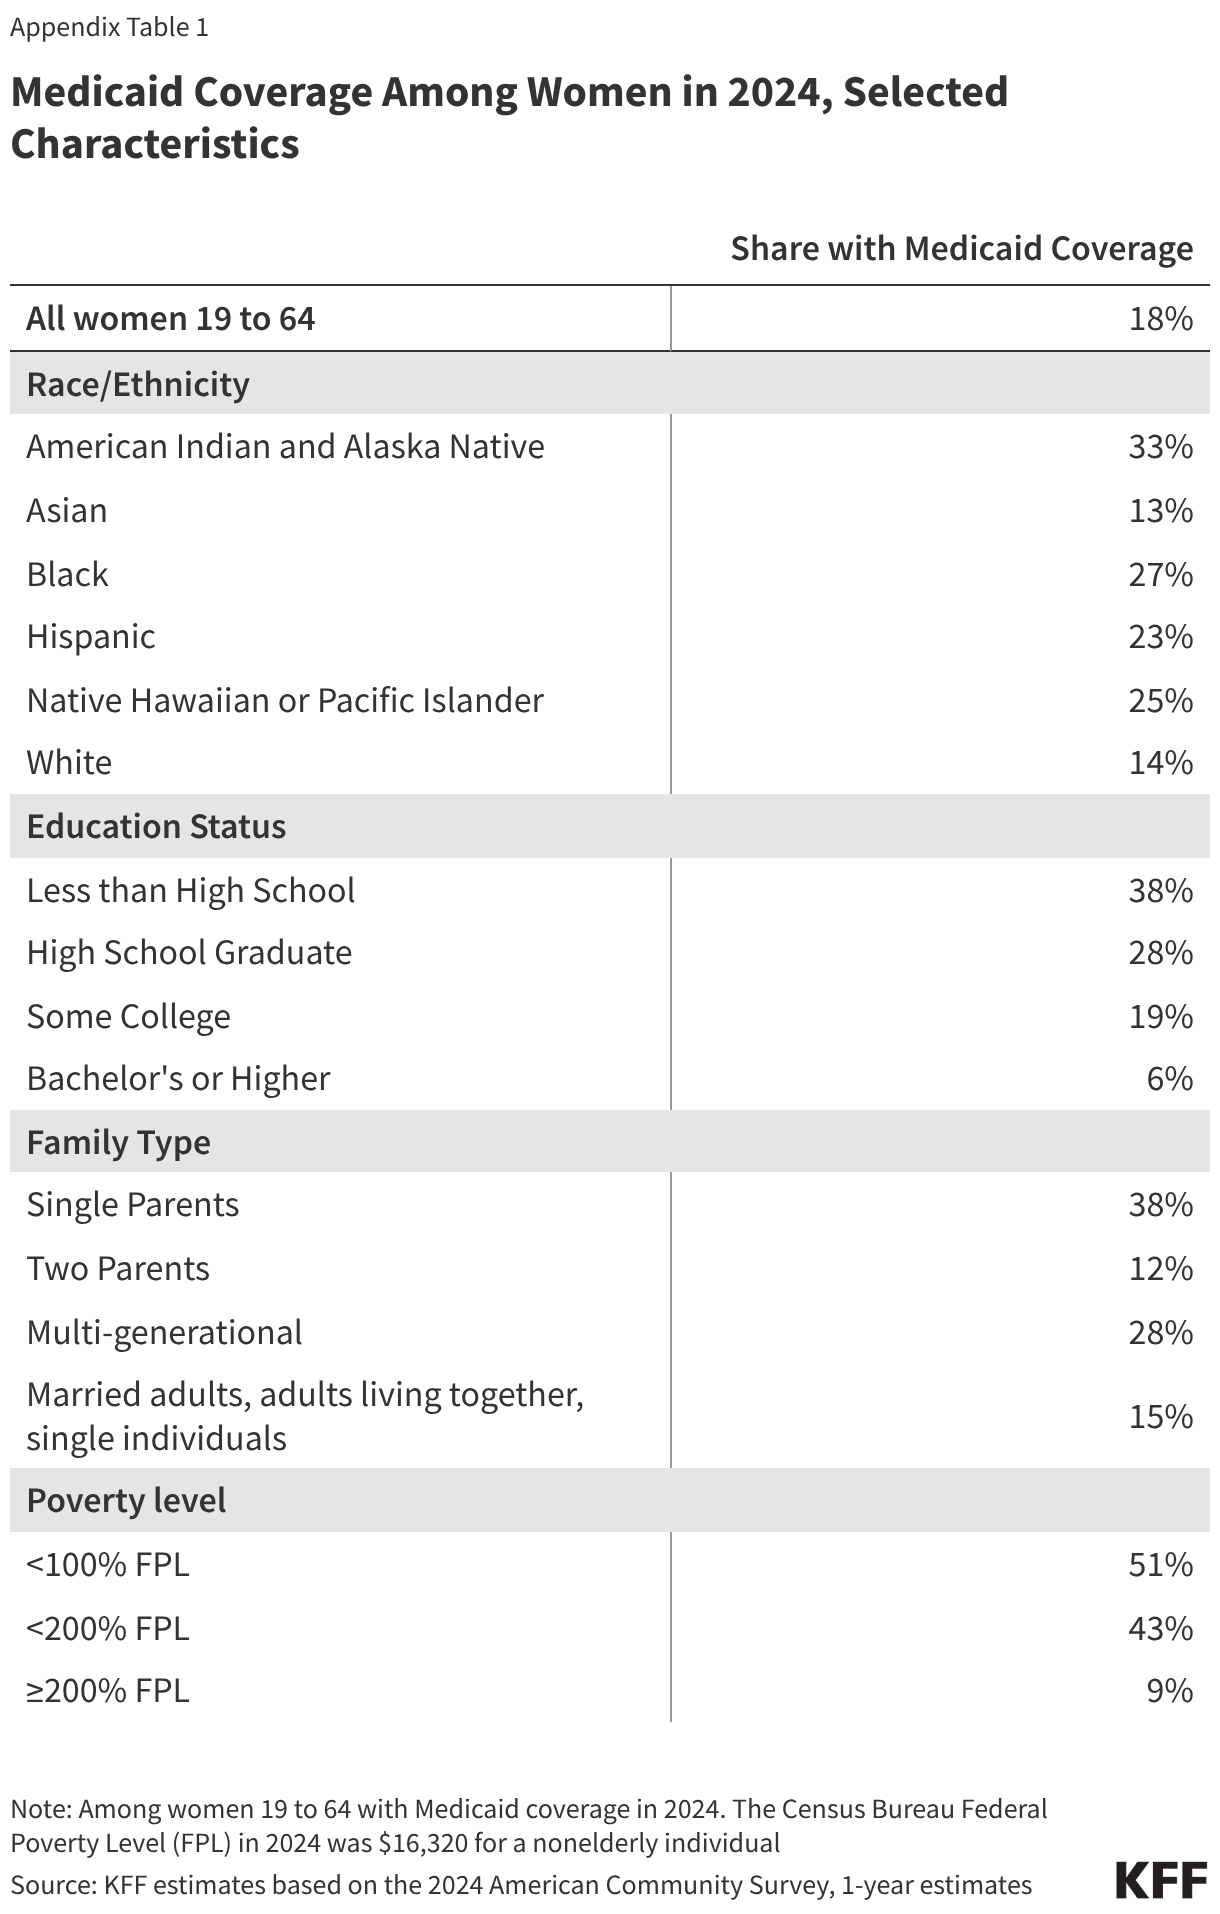
  • In 2024, Medicaid covered 18% of adult women ages 19 to 64 in the United States, but coverage rates were higher among certain groups, such as women of color, single mothers, low-income women, and women who have not completed a high school education (Figure 2).  
Bar chart showing the share of women ages 19 to 64 who are covered by Medicaid across various selected subgroups. Higher shares of women with lower incomes, single moms, and women of color are covered by Medicaid compared to the national average.
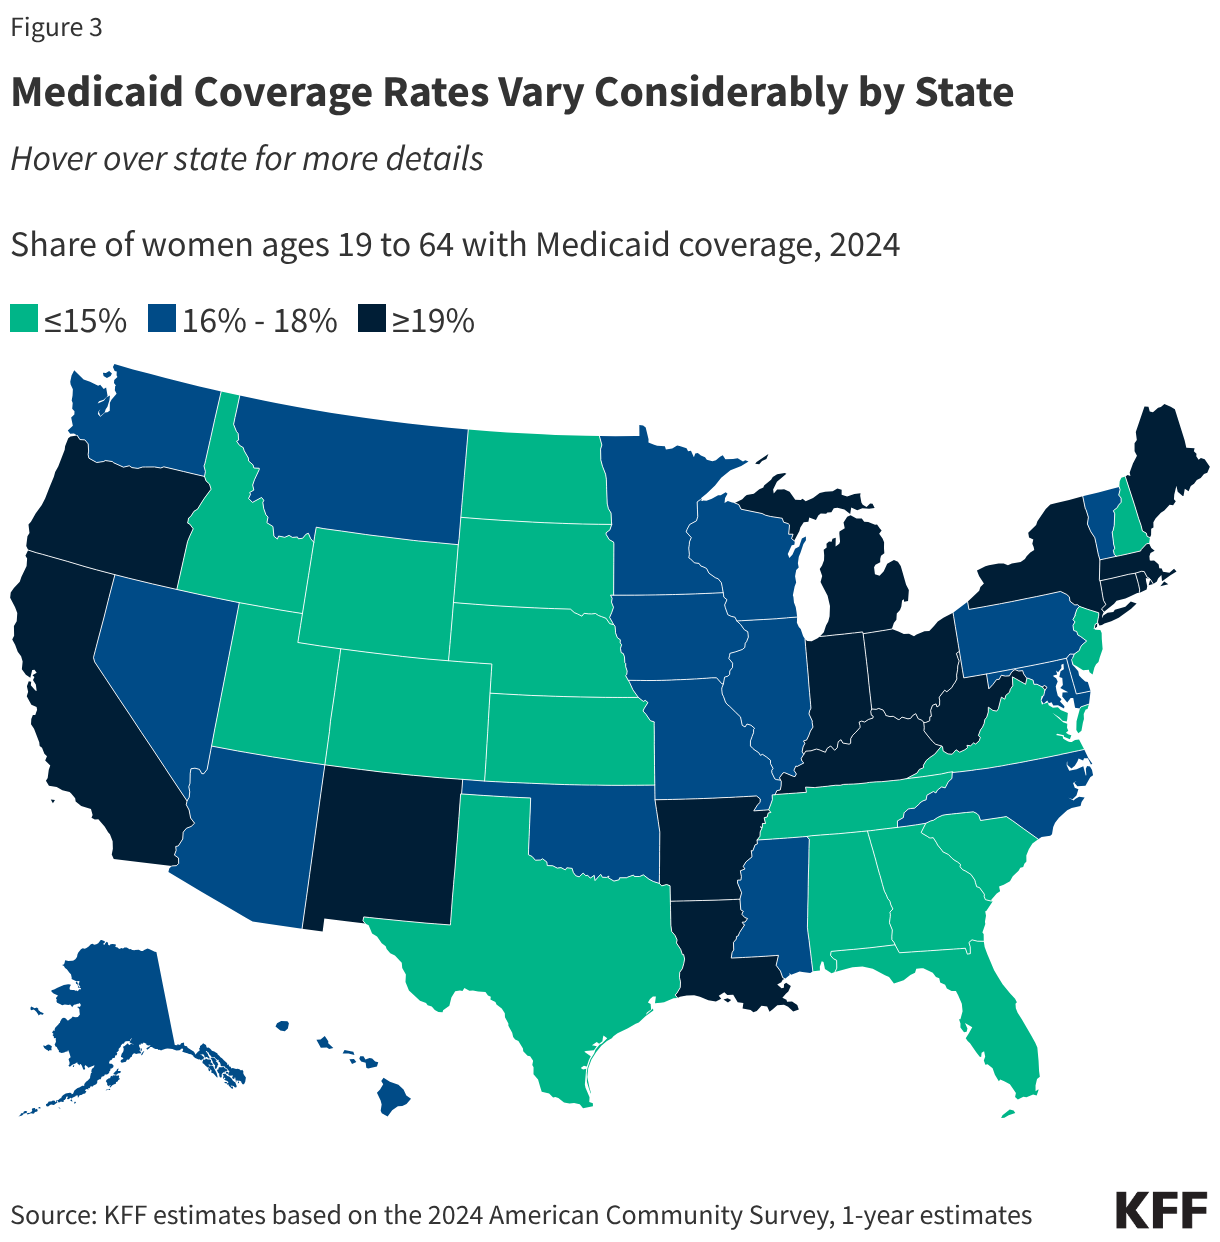
  • Differences in Medicaid eligibility levels and poverty rates across the states translate into vastly different Medicaid coverage rates for women across states, from a low of 9% in Utah and Texas to 32% in New Mexico (Figure 3).  
This map of the United States shows that Medicaid coverage among women ages 19 to 64 varies considerably across states. Coverage is highest in many states in the Northeast, Midwest, and West, while lower coverage is more common across parts of the South and Mountain West.

Adult women of reproductive age (19 to 49) comprise a quarter (24%) of the Medicaid population (Figure 1). Medicaid covers a wide range of reproductive health care services, including family planning, and pregnancy-related care including prenatal services, childbirth, and postpartum care—all without cost-sharing. Medicaid coverage of abortion services, however, is very limited under federal law and in most states.  

Family Planning 

Federal law requires state Medicaid programs to offer family planning benefits, but states determine the specific services and supplies for those who qualify through pre-ACA pathways. For the ACA expansion populations, the ACA requires states to cover all FDA approved, granted, and cleared  contraceptive methods, counseling on STIs and HIV, and screening for breast and cervical cancers. Research has found that most states have aligned their benefits and cover these services across all eligibility groups.  

  • The federal government pays 90% of costs for family planning services, a higher federal matching rate than for other services (typically between 50% and 78%). Women covered by Medicaid cannot be charged any out-of-pocket costs for family planning services. 
  • Federal law states that Medicaid beneficiaries have “free choice of provider,” which allows them to seek care from any qualified participating provider that offers the services. However, contrary to longstanding interpretation of the free choice of provider clause, a 2025 Supreme Court ruling, Medina v. Planned Parenthood South Atlantic, allows state Medicaid programs to disqualify clinics from participating in their networks if they offer abortion care in addition to other medical services. As of June 2026, at least seven states (AR, MO, MS, NE, OK, SC, and TX) have bans on Planned Parenthood’s participation in Medicaid, and several other states have proposed similar policies. Nationally, one in ten (10%) reproductive age women covered by Medicaid who received family planning services got their care at a Planned Parenthood clinic in 2023.
  • In addition to the Medina ruling, H.R.1 established a one-year ban on federal Medicaid reimbursements to Planned Parenthood in all states and some other reproductive health providers that provide abortion services. The policy was in effect from July 2025 to July 2026. While this rule expired, future legislation could be enacted by Congress to reinstate this funding ban.
  • Over half of states currently operate limited scope Medicaid family planning programs, which extend access to family planning services to uninsured women who do not qualify for full Medicaid coverage (often because their incomes exceed the Medicaid income thresholds).  

Maternity Care  

Medicaid is the largest single payer of pregnancy-related services, financing 40% of all U.S. births in 2024. In three states Medicaid covers more than 50% of all births. By federal law, all states provide Medicaid coverage without cost sharing for pregnancy-related services to pregnant people with incomes up to 138% of the federal poverty level (FPL), but many states extend eligibility to those at higher income levels. 

  • Similar to family planning, there is no federal definition of what services states must cover under their traditional Medicaid programs for pregnant women beyond inpatient and outpatient hospital care, but states that have expanded Medicaid eligibility must cover all preventive services recommended by the United States Preventive Services Task Force (USPSTF) to individuals who qualify through this pathway, which includes a broad range of pregnancy-related preventive services. Overall, most states cover a broad range of maternity care services, including prenatal screenings, folic acid supplements, and breastfeeding supports. States may not charge cost-sharing for any pregnancy-related services.
  • Historically, Medicaid coverage for pregnant people ended after 60 days. Due in part to the high rates of maternal mortality and morbidity in the United States and the disproportionately high rates of poor maternal outcomes experienced by Black and Native American pregnant people, there was a growing interest in expanding postpartum coverage beyond the 60 days. The federal American Rescue Act of 2021 gave states the option to extend postpartum coverage to pregnant people to a full year. To date, all states, with the exception of Arkansas, have extended postpartum coverage to 12 months.   
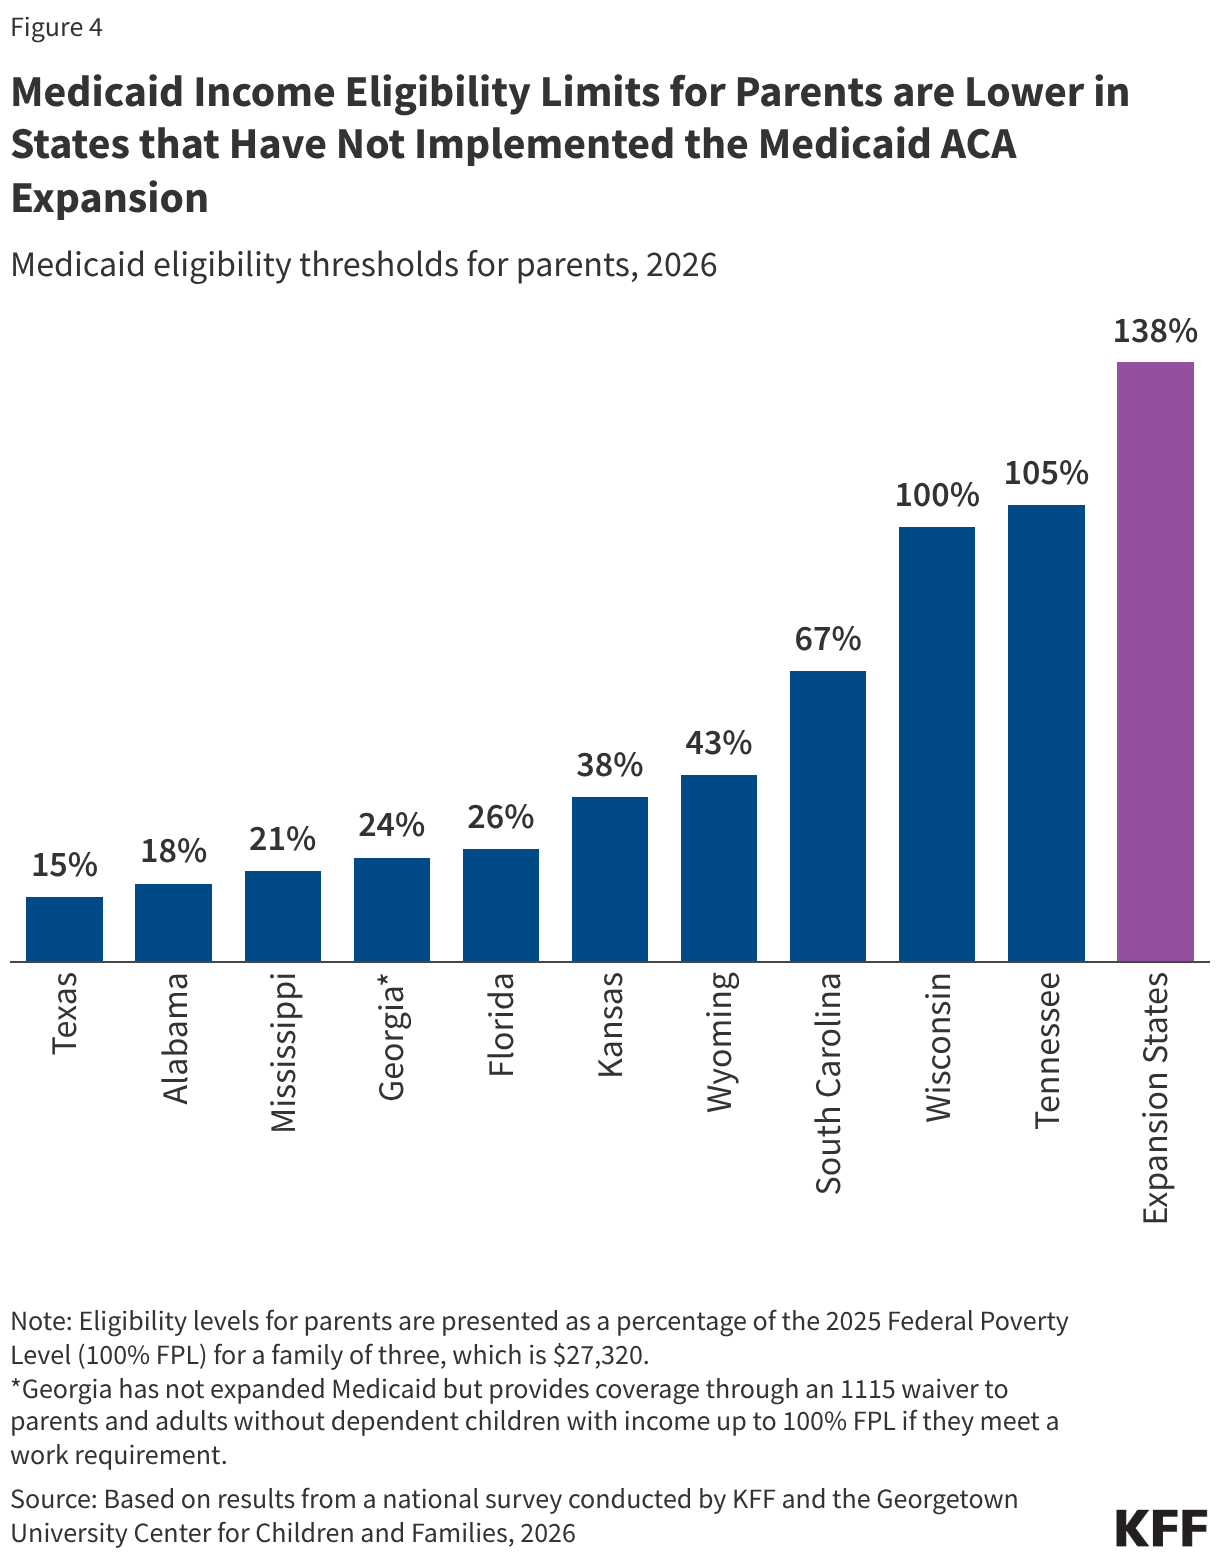
  • In the 10 states that have not expanded Medicaid coverage under the ACA, many women lose Medicaid eligibly after the postpartum period. This is because the income eligibility for pregnancy-related care is typically considerably higher than that offered to parents of dependent children. Eligibility levels for parents in the states that have not expanded Medicaid range from 15% FPL in Texas to 105% FPL in Tennessee (Figure 4). In the states that have expanded Medicaid eligibility, most women with Medicaid financed births are able to remain enrolled in the program and have continuous coverage beyond the postpartum period. 
Column chart showing that Medicaid income eligibility limits for parents are much lower in states that have not expanded Medicaid compared to states that have expanded Medicaid.

Abortion  

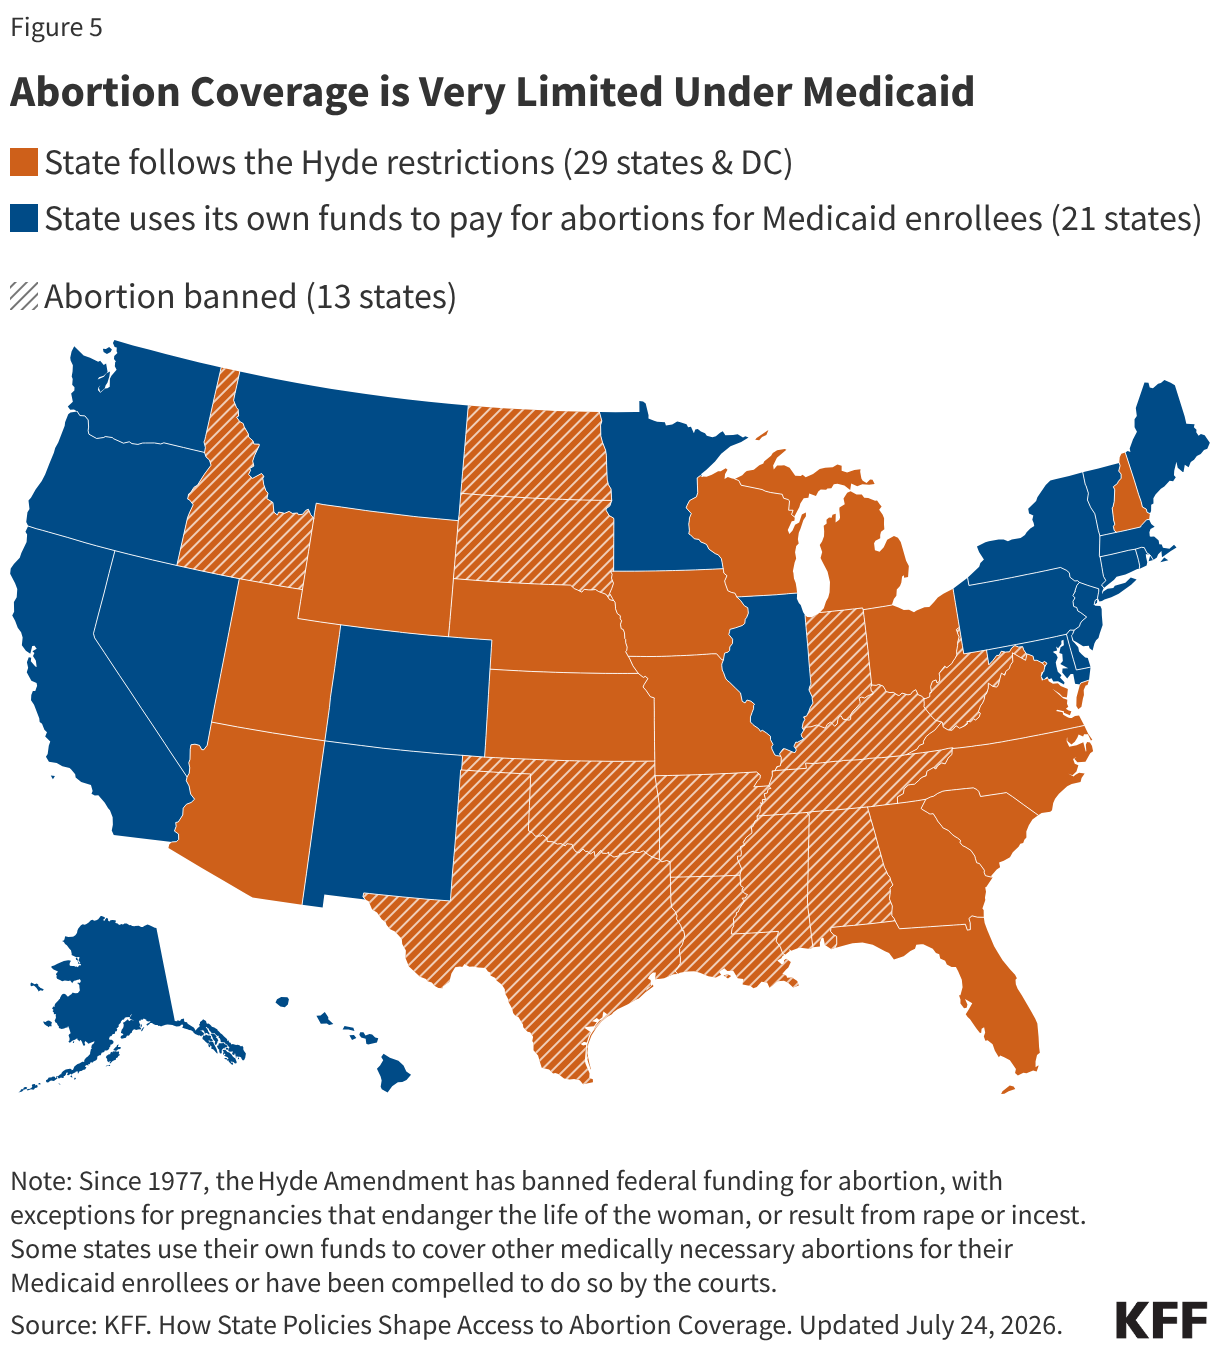
While the 2022 Dobbs decision overturning Roe v. Wade eliminated federal protections and allowed states to ban or severely restrict the provision of abortion, abortion remains legal and available in many states. However, the federal Hyde Amendment prohibits federal spending on abortions in all states, except when the pregnancy is a result of rape or incest, or when it jeopardizes the life of the pregnant person (Figure 5). States may use their own unmatched funds to cover abortions in other circumstances. As of July 2026, 29 states (including the 13 states where abortion provision is currently banned) and DC follow Hyde restrictions and 21 states cover abortions for Medicaid beneficiaries that are considered to be “medically necessary” and pay for these using only state funds. Nearly half of women of reproductive age with Medicaid coverage live in a state that follows Hyde amendment standards or currently bans the provision of abortion. In cases when Medicaid finances abortions for Medicaid enrollees, reimbursement rates tend to be low and often do not cover the full cost of the procedure.

This map shows that Medicaid coverage for abortion is very limited across the U.S. The majority of states, including the 13 states where abortion provision is banned, follow the federal Hyde restrictions and only cover abortions when the pregnant person's life in danger or the pregnancy is the result of rape/incest. Twenty-one states use their own funds to pay for abortions for Medicaid enrollees.

As women age, their health needs generally shift from reproductive care to greater need for screening and management of chronic diseases, mental health care, and disability care (although many women in their reproductive years also have these health needs).  

Mental Health  

  • In 2024, Medicaid covered over one in four (27%) adult women with any mental illness and 31% of adult women with a serious mental illness. 
  • Medicaid’s behavioral health benefits include acute care services, long-term services and supports to enable people with chronic illness to receive community-based care. In addition, states with Medicaid expansion programs are required to cover 10 essential health benefits, which include mental health and substance use disorder services, including behavioral health treatment.  

Breast and Cervical Cancers 

  • Under the Breast and Cervical Cancer Prevention and Treatment Act, states may extend Medicaid coverage for cancer treatment to uninsured women diagnosed with breast or cervical cancer through a federal screening program and receive a federal match for those services. In 2023, 44,000 women were enrolled in Medicaid through the Breast and Cervical Cancer Program.  
  • Preventive services for breast and cervical cancers are required benefits in ACA Medicaid Expansion programs. States are required to cover mammograms and pap tests, genetic (BRCA) screening for high-risk women, and breast cancer preventive medication for high-risk women. Most states cover the screening tests for all beneficiaries. However, coverage for other services such as such as colposcopy following an abnormal pap result (which will be a required as a covered services under the HRSA Women’s Preventive Services  Guidelines effective January 2027) and genetic screening for women at higher risk of breast cancer is more uneven across state eligibility pathways.  

Disability, Aging and Long-Term Care

Women with Disabilities  

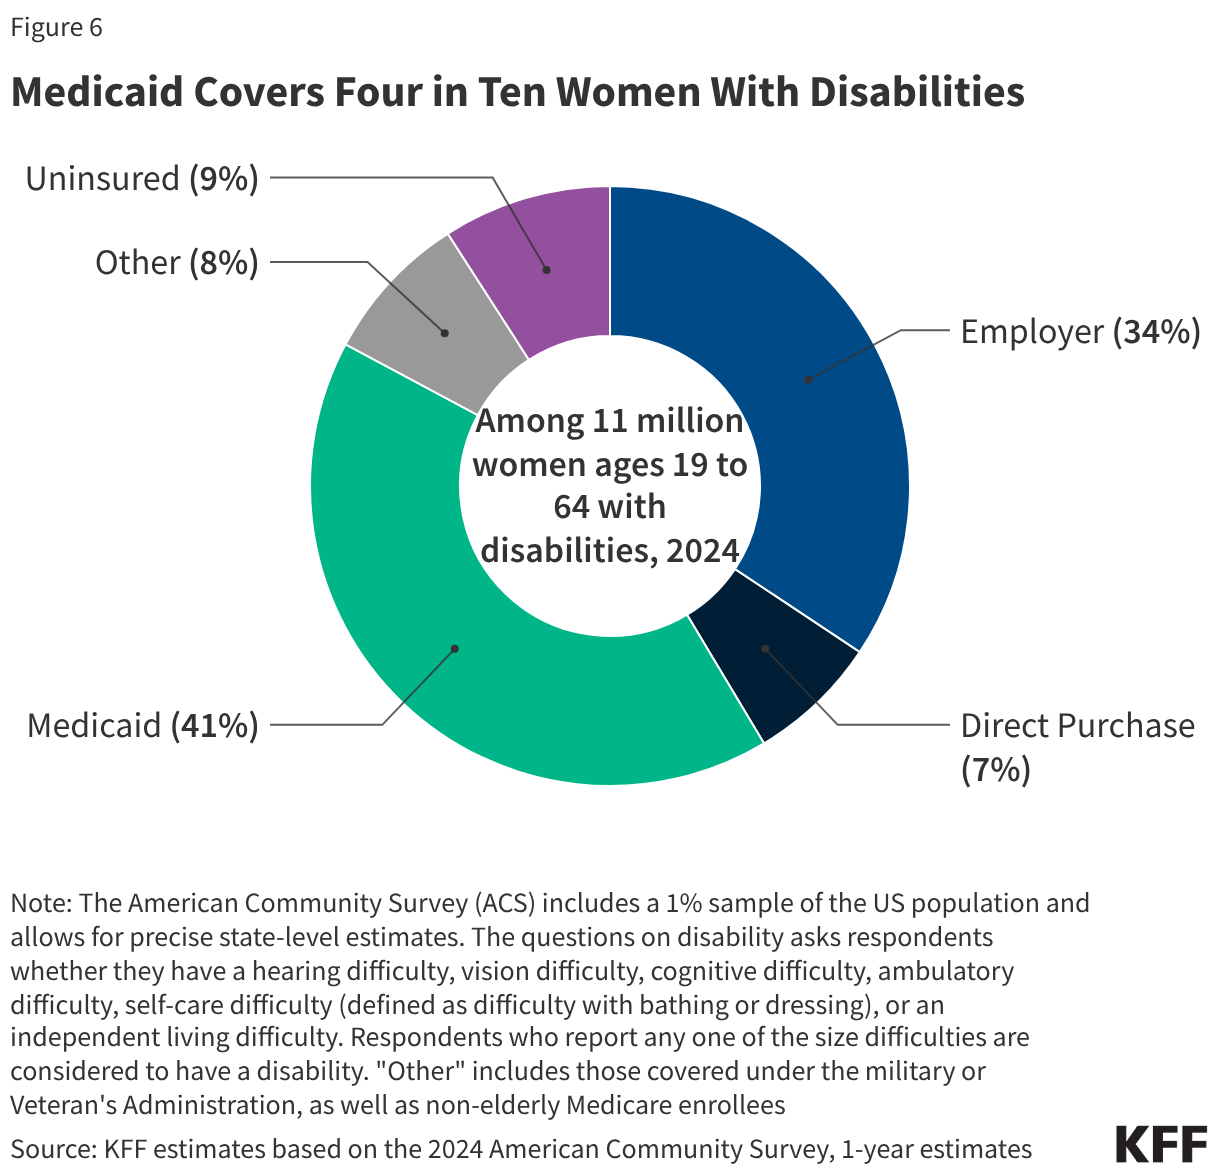
  • Medicaid covers four in ten (41%) nonelderly women who have a broad range of physical and mental disabilities, including physical impairments, severe mental illnesses, and specific conditions such as muscular dystrophy, cystic fibrosis, and HIV/AIDS (Figure 6).3 In addition, Medicaid also covers some nonelderly women who separately also qualify for Medicare coverage due to long-term disabilities (discussed below). 
  • Benefits that Medicaid covers include: assistance with medical and supportive services including rehabilitation, transportation, and therapeutic services, which help people with disabilities live independently and are not typically covered by private health insurance plans. Long-term services, including home health care, are another critical health benefit for women with disabilities that has very limited coverage through commercial plans but is covered by Medicaid.  
Pie showing health insurance coverage for women ages 19 to 64 with disabilities in 2024 in the U.S. Medicaid is a major source of coverage for women with disabilities, covering 41%, with another 34% getting coverage through employer-sponsored insurance.

Medicare-Medicaid Enrollees and Long-Term Care 

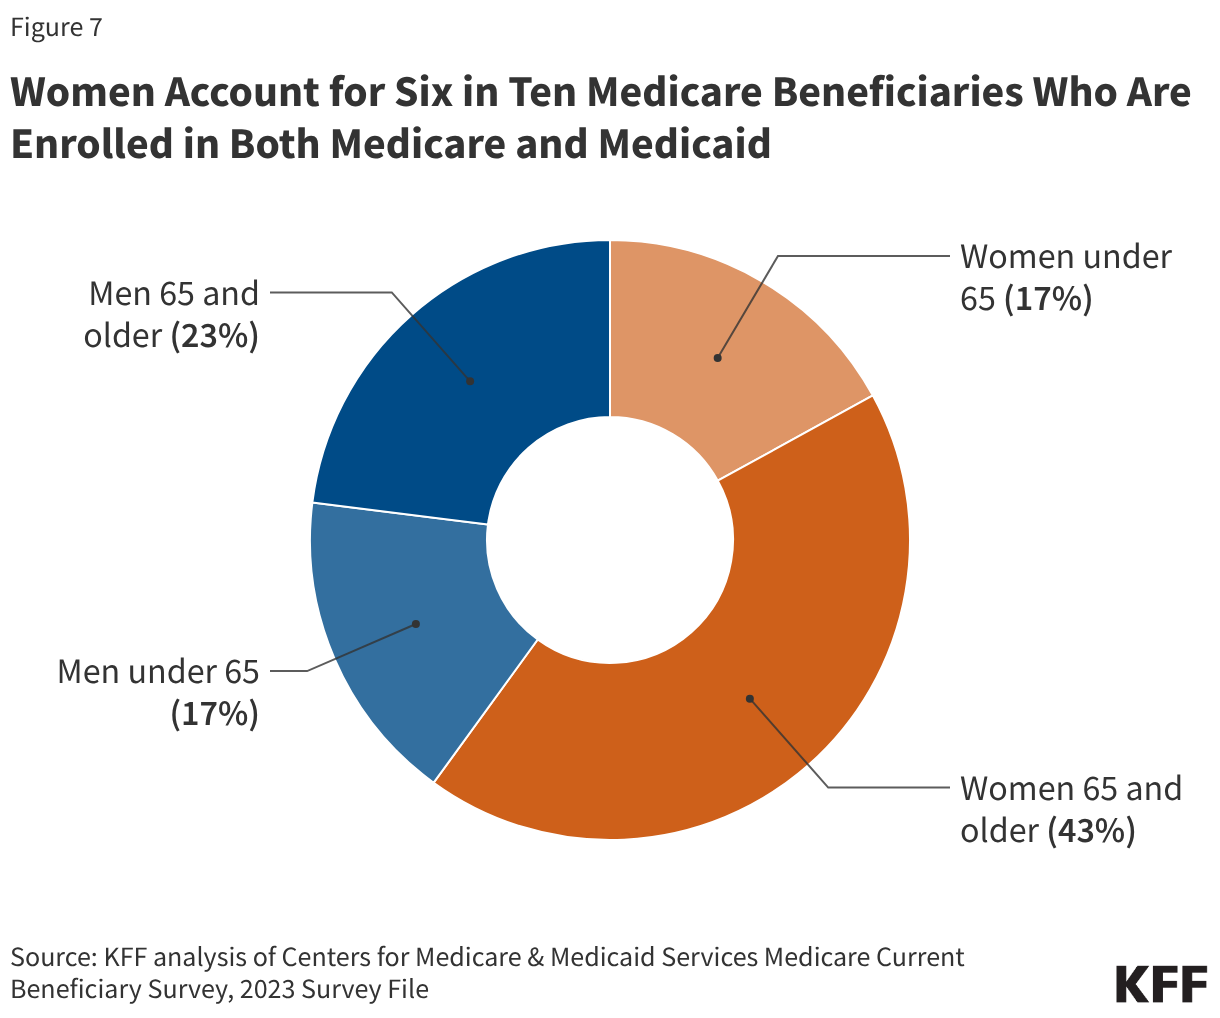
Medicare provides health coverage to people 65 and older and younger people with long-term disabilities. Medicaid provides coverage to approximately 12 million Medicare beneficiaries (20% of all Medicare beneficiaries) with low incomes and modest assets. These individuals are often referred to as “dually eligible beneficiaries,” and in 2023, women of all ages accounted for 60% of this group (Figure 7). Many of these beneficiaries have extensive and costly health needs.  

  • The majority of dually eligible beneficiaries qualify for full Medicaid benefits and may receive coverage for services that Medicare does not currently cover, such as dental and vision care, and long-term services and supports. Other dually eligible beneficiaries may only receive assistance with their Medicare premiums and/or cost sharing through the Medicare Savings Programs, but not full Medicaid benefits, if they meet an income and asset test. 
Women Account for Six in Ten Medicare Beneficiaries Who Are Enrolled in Both Medicare and Medicaid (Donut Chart)
  • Medicaid covers a continuum of long-term services and supports ranging from home care (HCBS) that allow persons to live independently in their own homes or in other community settings to institutional care provided in nursing facilities and intermediate care facilities for individuals with intellectual disabilities. In 2023, HCBS represented 64% of total Medicaid expenditures on long-term care (LTC).  
  • Since women are more likely to live longer and experience higher rates of chronic illness and disability than men, they are more likely to require long-term services in their lifetime. Approximately two-thirds of nursing home residents (61%) and people receiving home health care (60%) are women. Medicaid coverage provides access to these long-term services, which would otherwise be unaffordable for women with fixed incomes (in 2025, nursing home care averaged more than $114,975 annually for a semi-private room).  

Compared to their uninsured counterparts, women with Medicaid experience fewer barriers to care and on several measures have utilization rates comparable to low-income women with private insurance.  

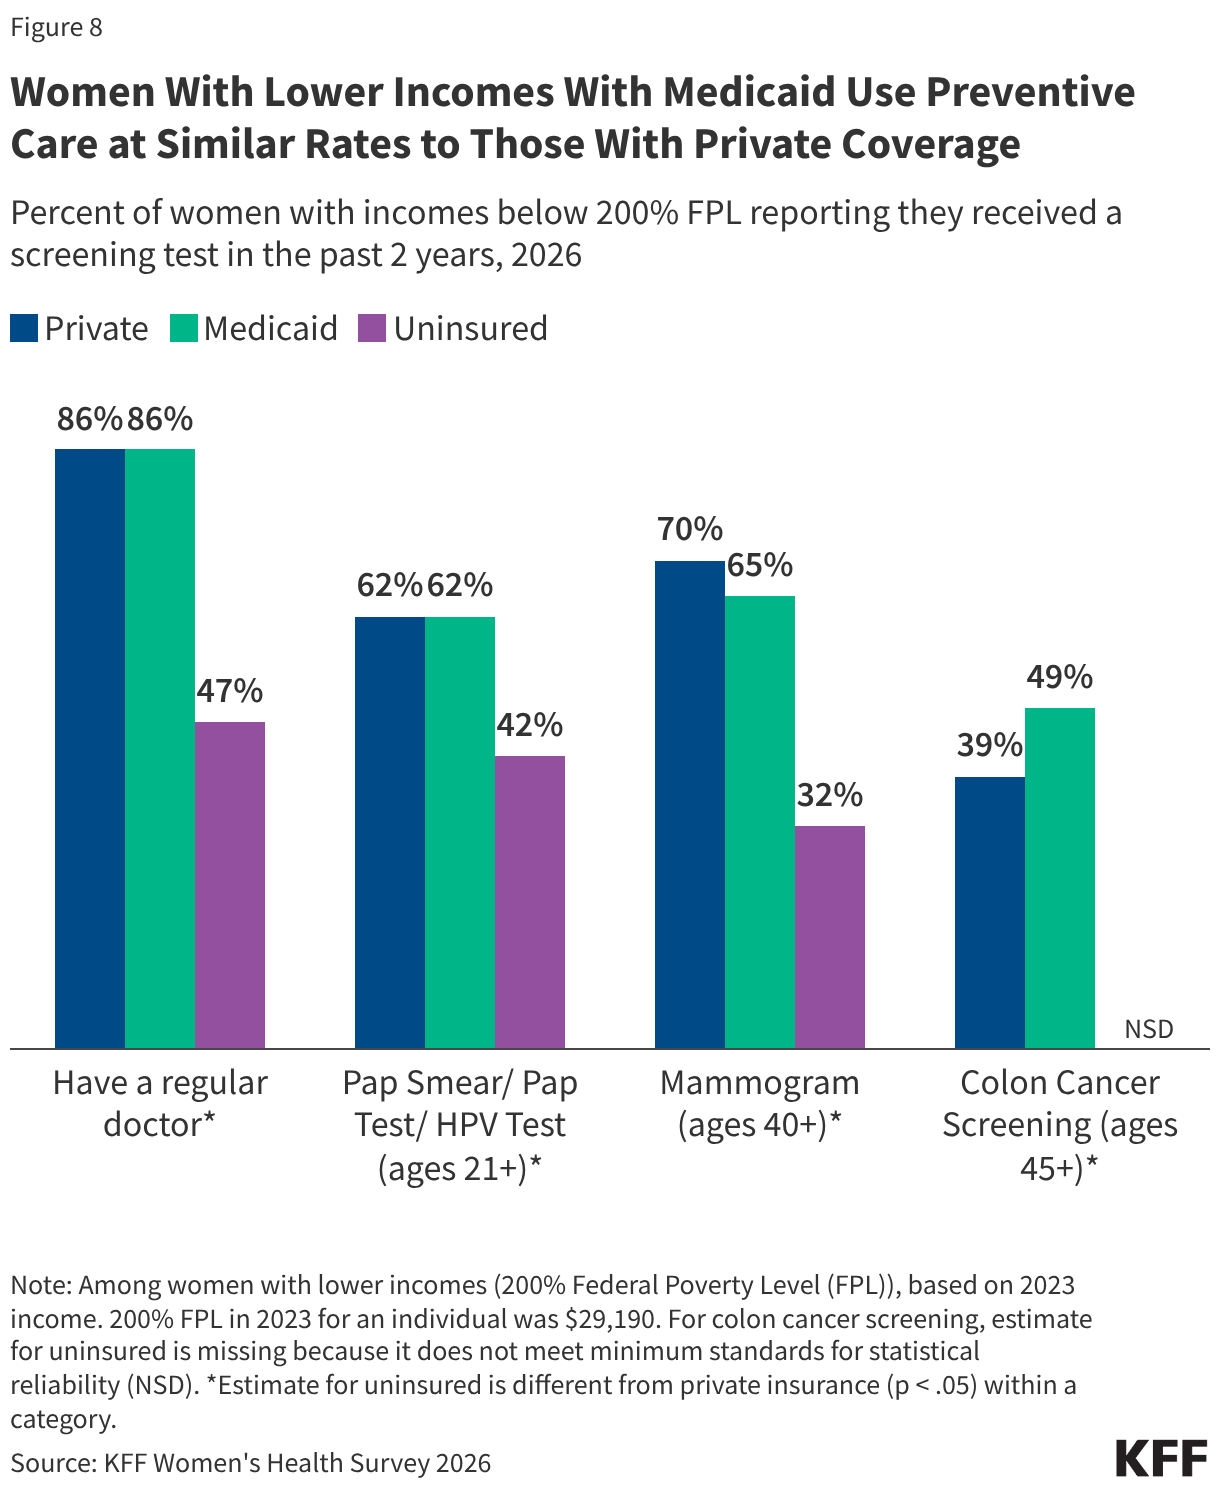
  • Women covered by Medicaid use primary and preventive health services, such as pap smears and mammograms, at rates comparable to women with private insurance and at higher rates than uninsured women (Figure 8).  
These grouped columns show that among lower-income women, those with Medicaid coverage are just as likely as women with private coverage to have a regular doctor and to receive Pap or HPV testing, and they report relatively high rates of mammograms and colon cancer screening. Uninsured women generally report lower rates of preventive care.
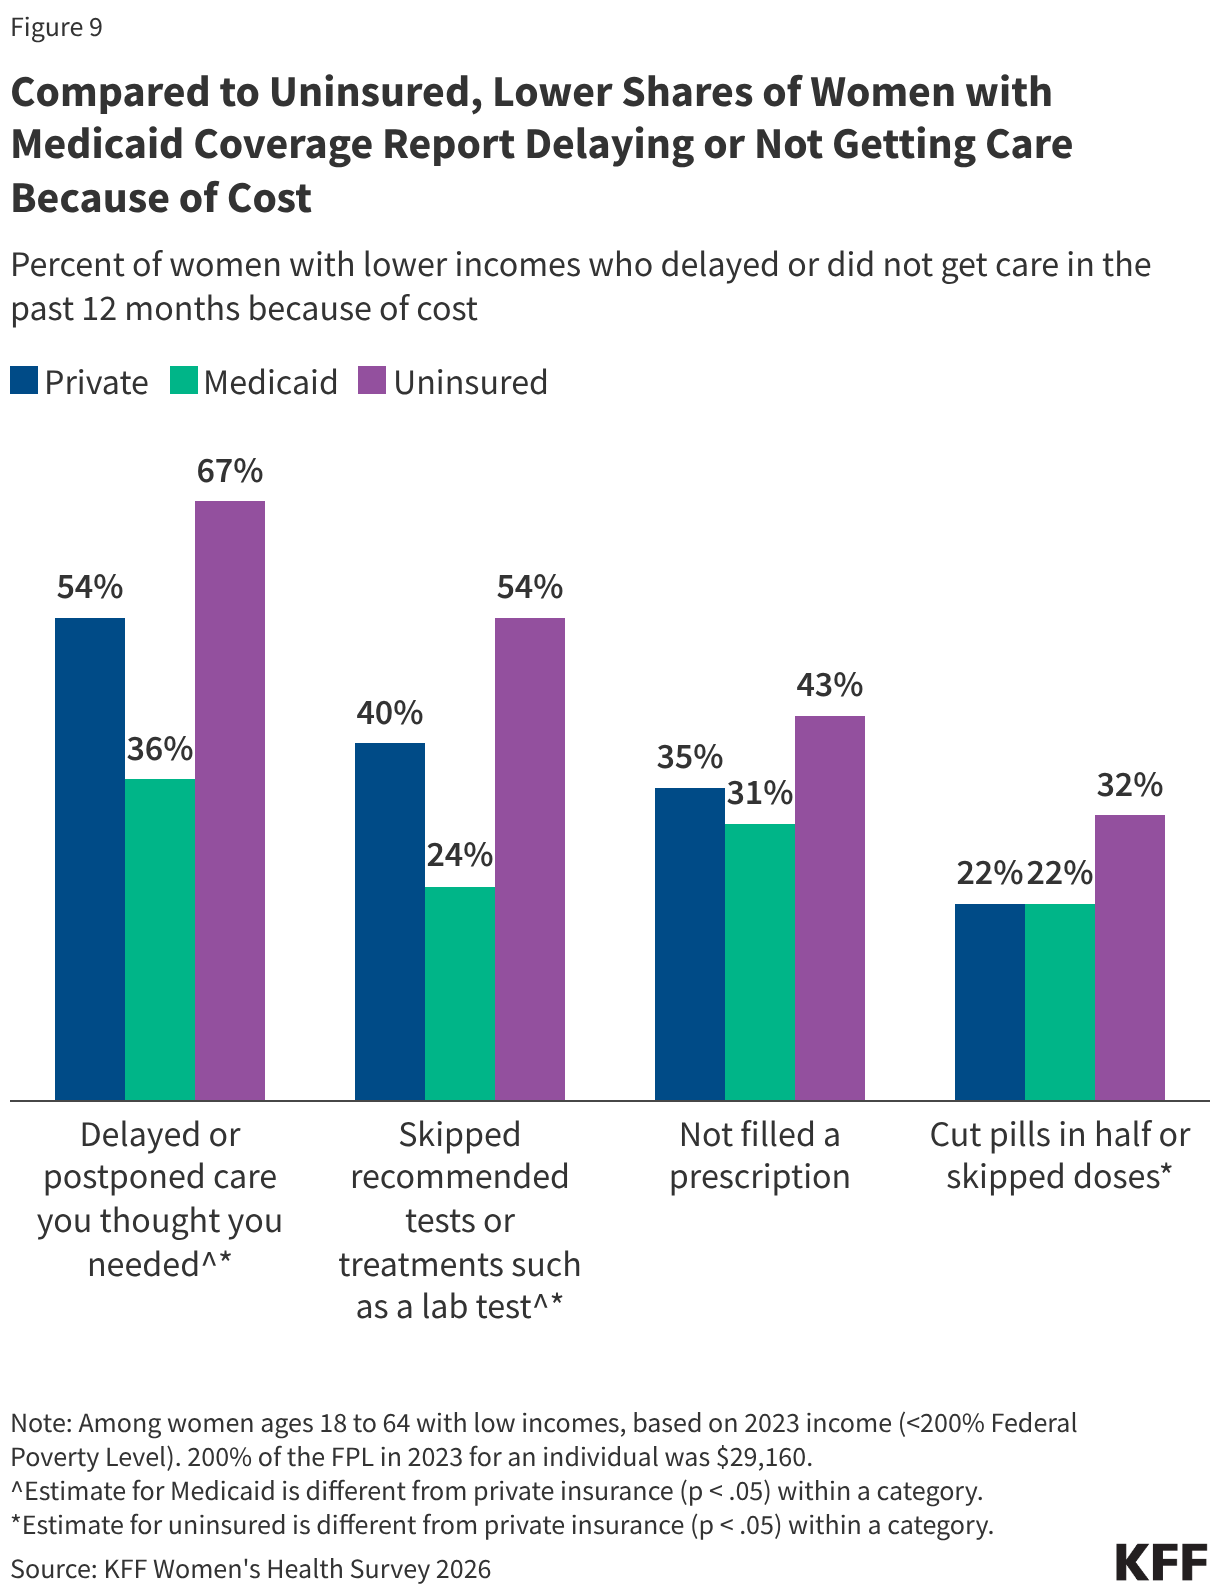
  • Women with Medicaid coverage are less likely than uninsured women to experience cost barriers. Compared to low-income women with private insurance, women on Medicaid were less likely to report that they delayed or went without care due to cost, likely attributable to the fact that Medicaid does not charge deductibles, rarely charges premiums and has only nominal cost-sharing. Affordability, however, is still a problem for some women in the program because they are typically low-income and have to pay out of pocket costs in states that impose caps on the number of covered visits or prescriptions or charge copayments for prescription drugs (for non-pregnant adults). Three in 10 low-income women on Medicaid report that they had not filled a prescription (31%) in the past year because of the cost (Figure 9).  
Grouped columns showing that among women with lower incomes ages 18 to 64, those with Medicaid coverage are less likely than uninsured women, and in some cases women with private coverage, to report delaying care, skipping recommended tests or treatments, or not filling prescriptions because of cost.
This table shows that Medicaid coverage among women ages 19 to 64 varies across racial and ethnic groups, education levels, family types, and income levels. Medicaid coverage is more common among women with lower incomes, those with less education, and single parents, as well as among American Indian and Alaska Native and Black women.
  1. KFF analysis of the T-MSIS Research Identifiable Files, 2023 (Preliminary) ↩︎
  2. KFF analysis of the T-MSIS Research Identifiable Files, 2023 (Preliminary) ↩︎
  3. KFF estimate based on the 2024 American Community Survey, 1-year estimates ↩︎

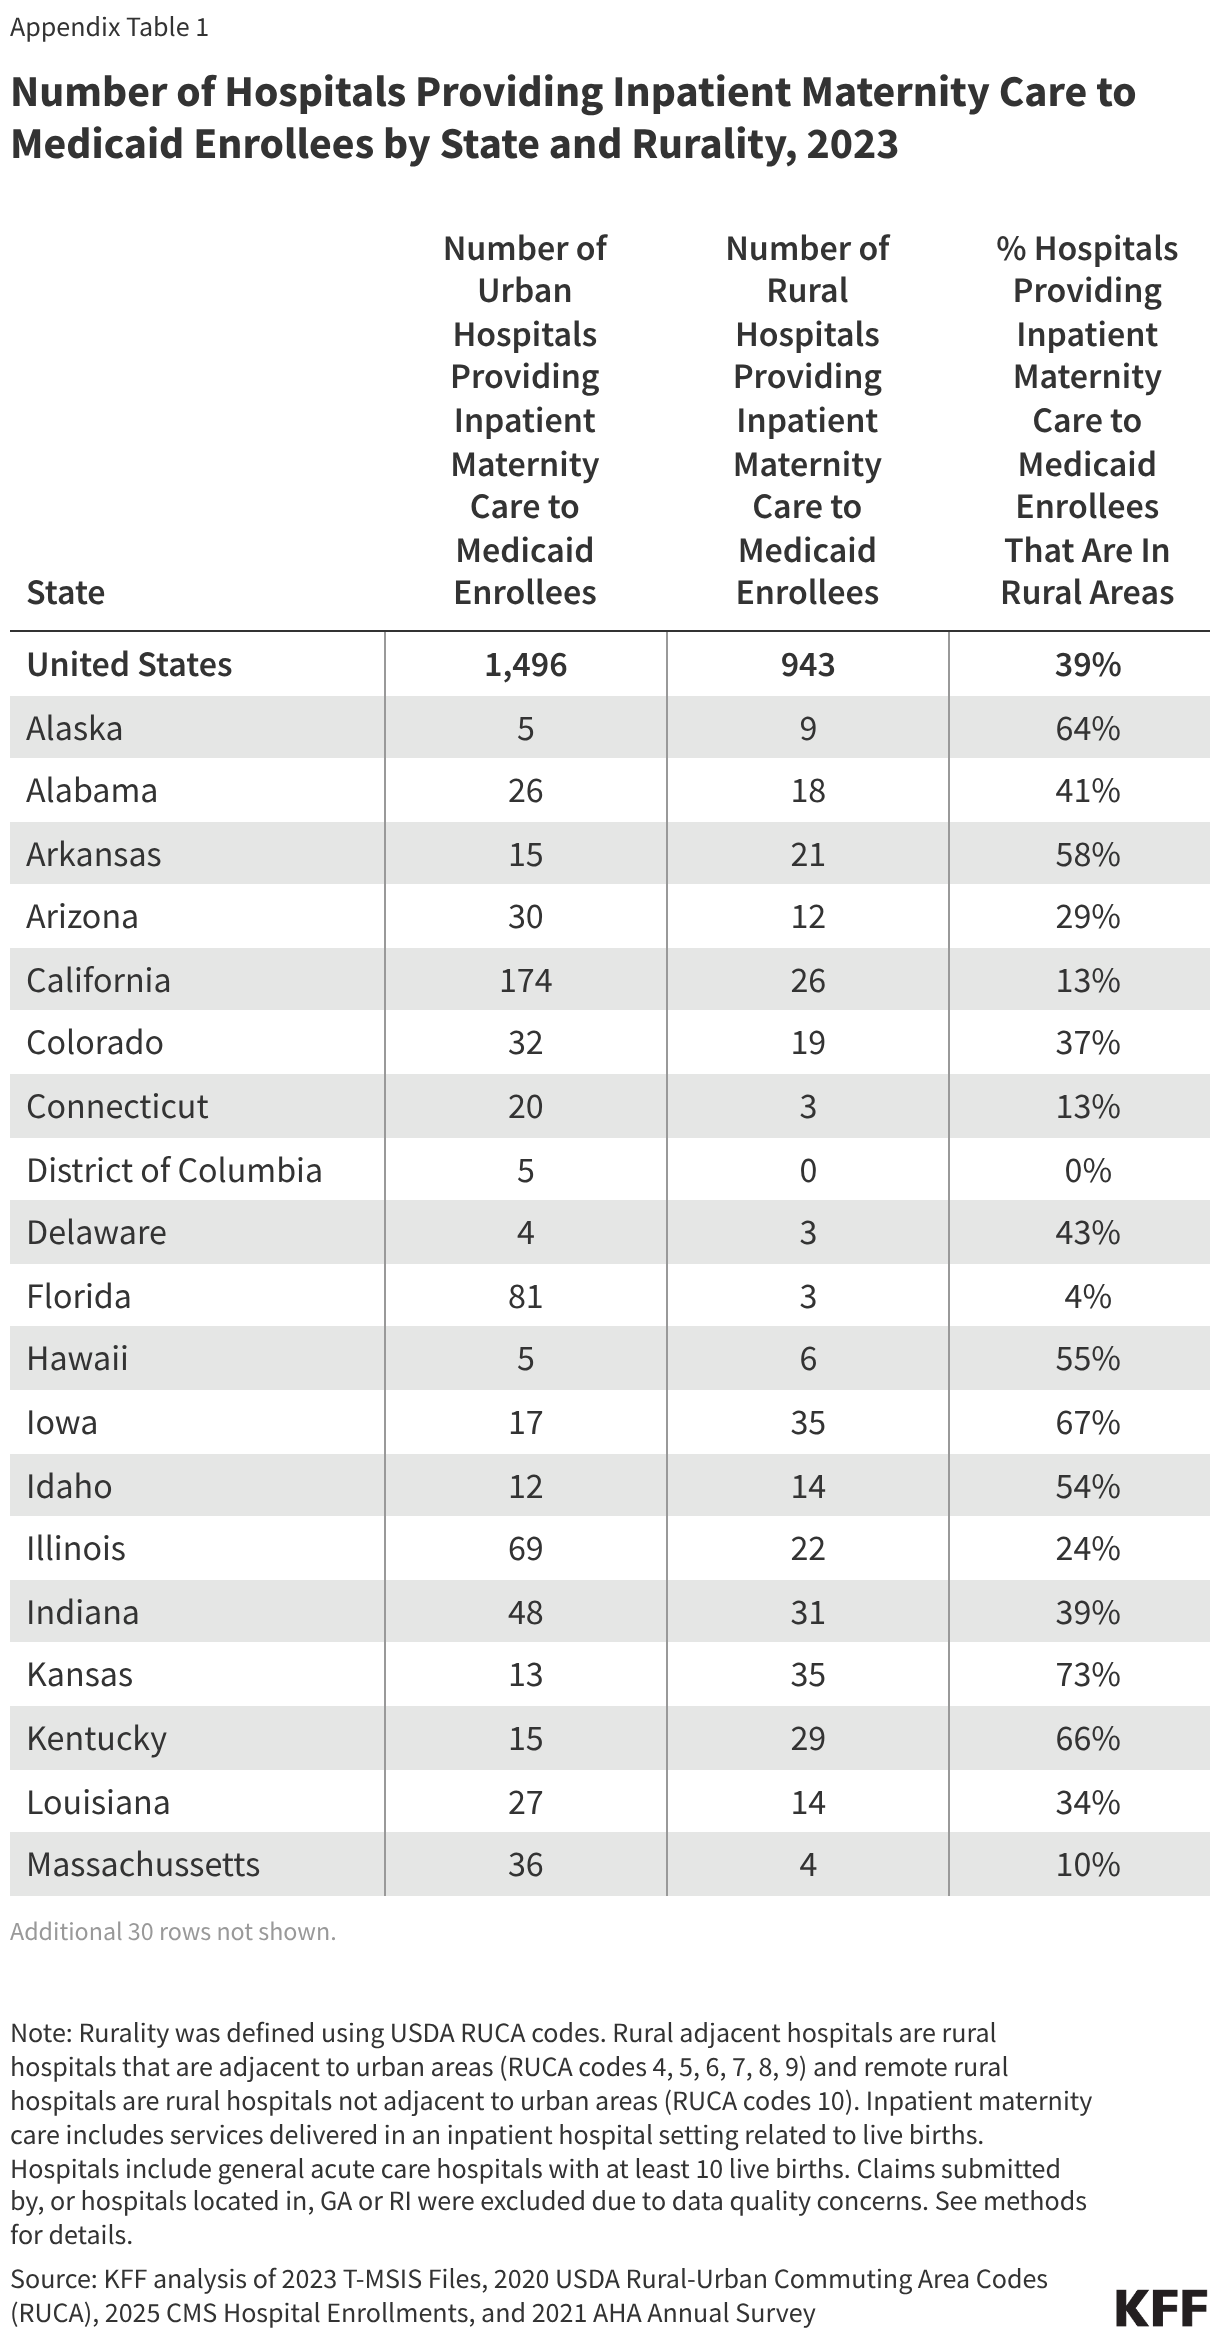
Availability of Rural Hospitals Providing Inpatient Maternity Care in Medicaid

Published: Aug 26, 2026

In recent years, concerns about access to maternity care in rural areas have grown as hundreds of rural hospitals have closed their obstetrics units. In 2023, approximately half of rural hospitals offered obstetrics services, and almost half of rural counties did not have a hospital offering obstetrics services. A lack of access to maternity care can lead to negative health outcomes, such as low birthweight and premature births, and increased maternal mortality. According to a Government Accountability Office study, difficulty recruiting and retaining providers and low Medicaid reimbursement rates are some of the biggest challenges to providing obstetric services in rural areas. Medicaid is a major payer of obstetrics care in rural communities, covering almost 1 in 4 rural women of reproductive age and financing nearly half of all births in rural communities.

Existing concerns for hospital-based rural maternity care access are expected to grow due to cuts to Medicaid in the 2025 reconciliation law that are projected to reduce spending in rural areas through changes to hospital supplemental payments and reduced Medicaid enrollment. Although increasing obstetric payments to hospitals has been a priority for many states over the past decade, changes from the reconciliation law could result in reduced Medicaid revenues for hospital services, including for rural hospitals that already have lower financial margins. While the temporary rural health fund included in the law allocates $50 billion over ten years to reduce the impact of the Medicaid cuts in rural areas, not all of it is directed to rural hospitals and, overall, it is not likely to offset the longer-term impacts of the cuts.  

Considering the existing challenges to hospital-based maternity care in rural areas and the potential for worsening trends, this brief analyzes the availability of hospitals providing inpatient maternity care in rural areas for Medicaid enrollees and illustrates how access to these services could be affected if additional rural hospitals were to close or eliminate those services. For the purposes of this data note, hospitals offering inpatient maternity care are defined as those that delivered 10 or more births in the year (see Methods).

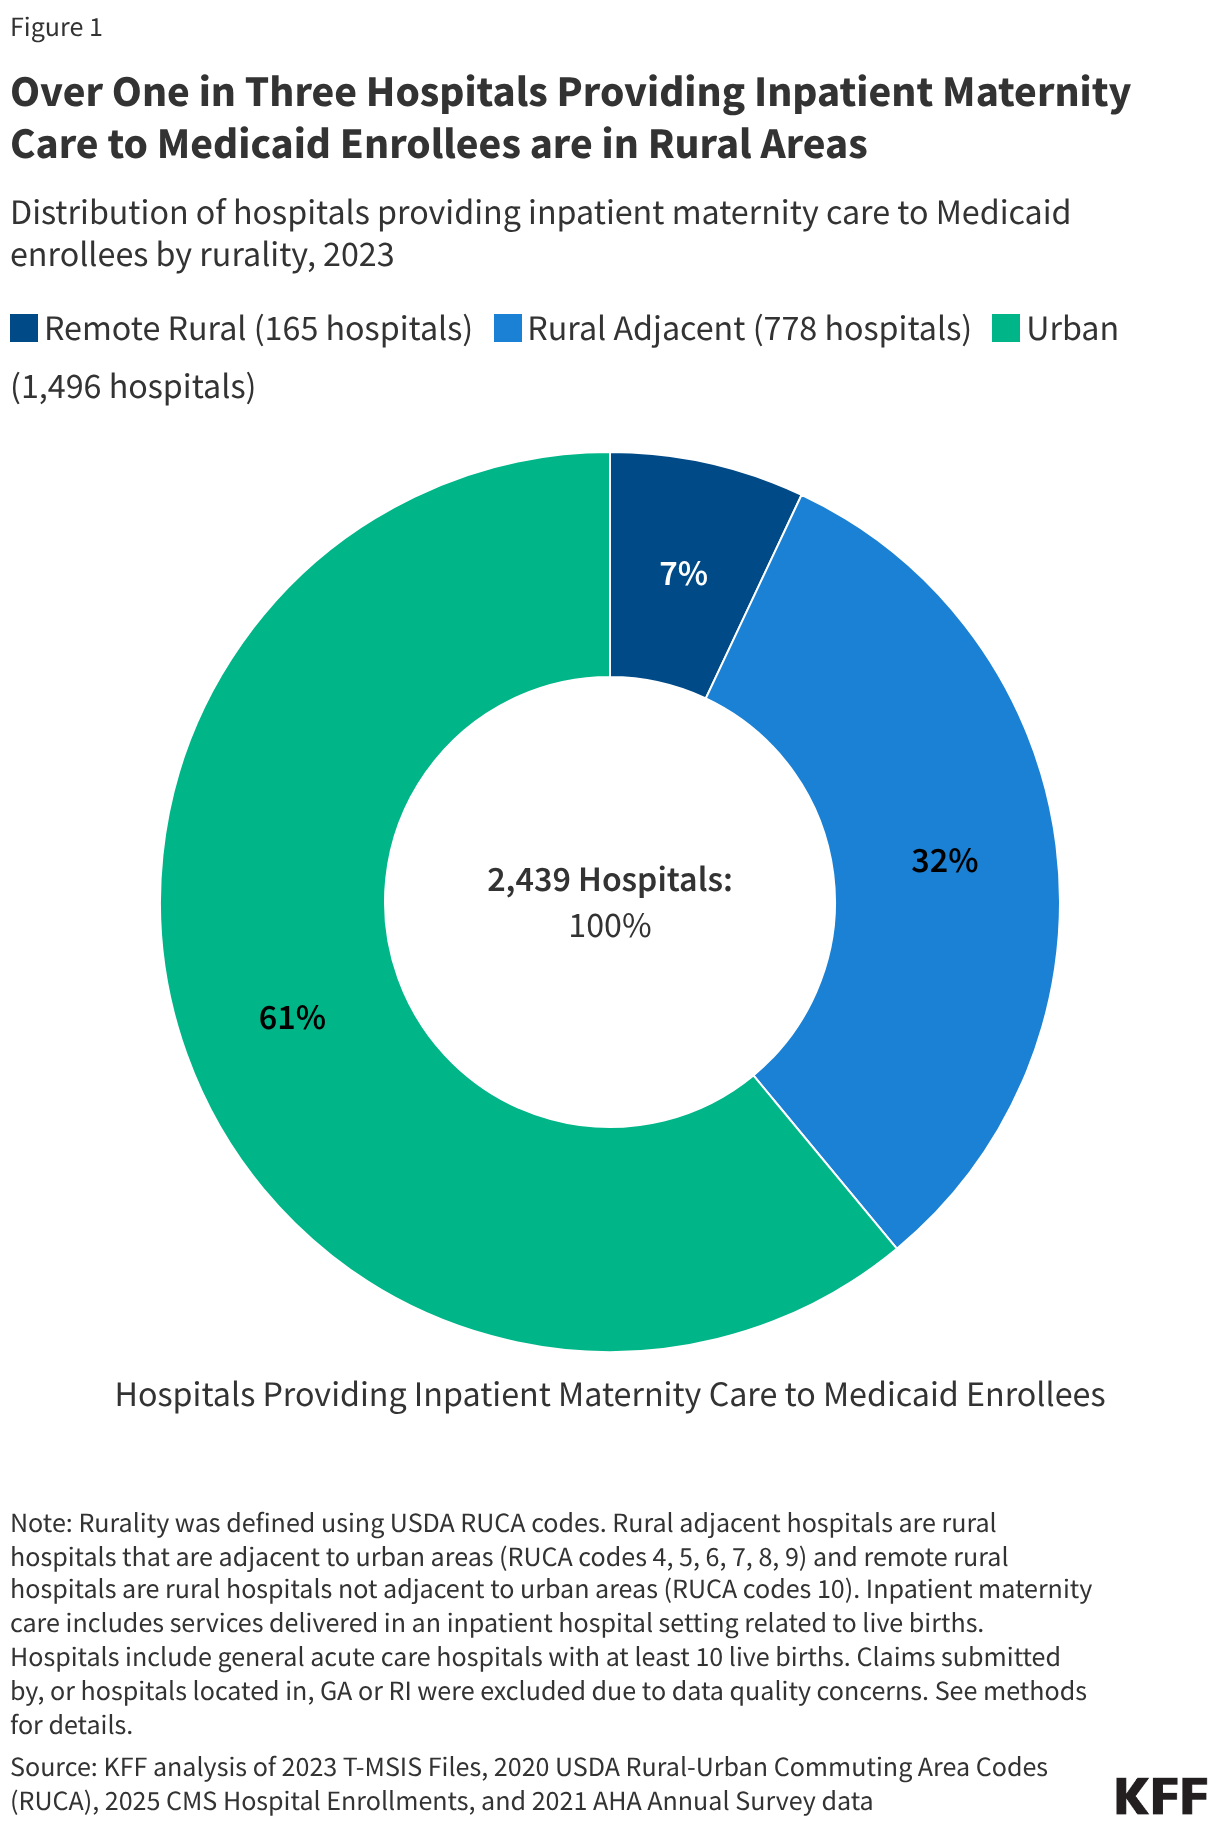
Over 1 in 3 hospitals providing inpatient maternity care to Medicaid enrollees are in rural areas.

In 2023, 943 rural hospitals provided inpatient maternity care to Medicaid enrollees, constituting 39% of hospitals nationally providing inpatient maternity care to Medicaid enrollees. Rural hospitals that were adjacent to urban areas (rural adjacent) accounted for 778 (32%) hospitals, and the most rural hospitals (those not adjacent to urban areas, remote rural) accounted for 165 (7%) hospitals (Figure 1).

Over One in Three Hospitals Providing Inpatient Maternity Care to Medicaid Enrollees are in Rural Areas (Small multiple donut chart)

Rural hospitals providing inpatient maternity care to Medicaid enrollees are typically located more than 40 minutes from the closest in-state hospital providing inpatient maternity care.

If a rural hospital closes, one measure of the effect on Medicaid enrollees is the amount of time it would take to drive to the nearest in-state hospital. The typical drive time between hospitals providing inpatient maternity care to Medicaid enrollees and their closest in-state neighbors is 43 minutes for rural hospitals compared with 13 minutes for urban hospitals (Figure 2). For 1 in 4 of these rural hospitals, the nearest in-state hospital that provided inpatient maternity care is at least one hour away (Figure 2). Distance to the nearest in-state hospital was calculated because most Medicaid enrollees obtain medical services within their state of residence, and though states have special processes for enrolling and paying out-of-state hospitals, seeing providers across state lines is challenging for enrollees (see Methods). The analysis uses driving time (in minutes) as a measure of distance between two hospitals because it accounts for traffic patterns between rural and urban areas, but results are similar when using other measures of distance (Appendix Figure 1).

Rural Hospitals Providing Inpatient Maternity Care to Medicaid Enrollees are Typically Located More Than 40 minutes from the Closest In-State Hospital Providing Inpatient Maternity  Care (Dot Plot)

Typical drive times from rural hospitals providing inpatient maternity care to Medicaid enrollees to the closest in-state hospital providing inpatient maternity care vary by state.

In 14 states, the typical drive time from rural hospitals providing inpatient maternity care to Medicaid enrollees to their nearest in-state neighbor is one hour or more (Figure 3).The top three states with the longest typical driving times are Alaska, Nevada, and North Dakota. The states with the shortest drive times between their rural hospitals and another hospital providing inpatient maternity care to Medicaid enrollees are New Jersey, Louisiana, and Ohio.

Typical Drive Times From Rural Hospitals Providing Inpatient Maternity Care to Medicaid Enrollees To The Closest In-State Hospital Providing Inpatient Maternity Care Vary by State (Choropleth map)

Patrick Drake, an independent consultant, contributed to the analysis of driving time data.

Appendix

Comparison of Different Hospital Distance Measures (Dot Plot)
Number of Hospitals Providing Inpatient Maternity Care to Medicaid Enrollees by State and Rurality, 2023 (Table)

Methods

Data: This analysis uses data available from the 2023 Preliminary T-MSIS Research Identifiable Demographic-Eligibility and Claims Files. The Inpatient (IP) Header File was used to identify hospitals providing inpatient maternity care to Medicaid enrollees.

State Inclusion Criteria: To assess the usability of states’ data, four relevant quality assessments from the DQ Atlas were examined for IP claims file and billing provider completeness. KFF also evaluated usability based on the percentage of hospitals that merged with two external data sources used in the analysis for hospital addresses (CMS Hospital Enrollments and AHA Annual Survey data). The billing provider National Provider Identifier (NPI) is the primary hospital identifier in the claims data for this analysis (see more details under “Identifying Hospitals”). Below are the states that were excluded according to each criterion:

  • DQ Atlas Claims Volume – IP: No states excluded
  • DQ Atlas Service Users – IP: No states excluded
  • DQ Atlas Billing Provider NPI – IP: Georgia was deemed “unusable” for this assessment and excluded. Approximately 81% of its IP Header claims were missing a billing provider NPI.
  • DQ Atlas Billing Provider Type, Specialty, and Taxonomy – IP: No states excluded
  • KFF state-level merge rates to CMS Hospital Enrollments and AHA Annual Survey data: Rhode Island was excluded. Approximately 44% of its IP Header claims were unable to merge onto either the CMS Hospital Enrollments or the AHA Annual Survey data, and thus hospital address could not be determined (other states, except Georgia, had 15% or less of their claims unable to merge).

Identifying Inpatient Maternity Care: A hospital was identified as providing “inpatient maternity care” when it provided 10 or more live births to Medicaid enrollees, following other studies on obstetric care access in rural areas. Diagnosis and procedure codes in the T-MSIS inpatient header claims files were used to identify live birth codes from the Office of Population Affairs’ published code lists for the Contraceptive Care Measures that are endorsed by CMS’ consensus-based entity. A list of diagnosis and procedure codes is available upon request.

Identifying Hospitals: Hospitals were identified in the claims data using billing provider NPI. According to DQ Atlas methodology, the billing provider in the IP file primarily represents the hospital where the inpatient care occurred.

Hospital address information: This analysis used data available from the 2025 CMS Hospital Enrollments (accessed in November 2025) and data available from FY2021 AHA Annual Survey (accessed in February 2023) to identify hospital addresses. The CMS Hospital Enrollments data set provides monthly enrollment information for all hospitals currently enrolled in Medicare and the AHA Annual Survey provides data from an annual survey of all hospitals in the U.S. and its associated areas. KFF used both sources to account for hospitals that may have closed between 2023 and 2025 or opened between 2021 and 2023 (2023 was the most current year of T-MSIS data at the time of analysis).

The analysis used these external sources rather than the T-MSIS Annual Provider File (APR) because of concerns regarding data quality in the APR file. Technical documentation for the APR suggests that users may want to use the NPI to link to external data sources to obtain additional provider information, and other researchers have found provider legal name and address in the APR to be inconsistent.

Hospital exclusion criteria: Below is a list of criteria used to identify hospitals providing inpatient maternity care to Medicaid enrollees in the analysis. The number of unique NPIs and the number of IP Header claims that were kept after each step are reported.

Only hospitals identified as a general acute care hospital using National Plan and Provider Enumeration System (NPPES) taxonomy codes were included in the analysis because they are accessible to all Medicaid enrollees and treat a range of health care conditions. Hospital types that were excluded from the analysis include: chronic disease hospitals, long-term care hospitals, religious nonmedical health care institutions, psychiatric hospitals, rehabilitation hospitals and military hospitals.

Exclusion Criteria# of Unique Billing Provider NPIs Remaining# of IP Header Claims
Start: All unique billing provider NPIs/header claims in the IP file10,973 (100%)12,267,627 (100%)
Claims without a live birth diagnosis or procedure code3,132 (7,841 dropped)1,715,496 (10,552,131 dropped)
Submitting state for the claim is GA or RI (see “State Inclusion Criteria”)2,995 (137 dropped)1,648,650 (66,846 dropped)
Billing provider NPI is associated with a RI, GA or PR zip code2,953 (42 dropped)1,646,590 (2,060 dropped)
Billing provider NPI is missing or less than 10 digits2,951 (2 dropped)1,644,384 (2,206 dropped)
Billing provider taxonomy code is not a general acute care hospital or is missing2,675 (276 dropped)1,626,606 (17,778 dropped)
Did not merge onto CMS Hospital Enrollments or AHA Annual Survey data2,596 (79 dropped)1,600,273 (26,333 dropped)
Claim is not for a Medicaid eligible enrollee (CHIP_CD = 1 or, if missing, ELGBLTY_GRP_CD = 1-60 or 69-75) or with a Medicaid claim type code (CLM_TYPE_CD = 1 or 3).2,595 (1 dropped)1,466,715 (133,558 dropped)
NPIs that correspond to the same hospital address/coordinates/CCN2,537 (58 dropped)1,466,715 (claims not dropped since they represent the same hospital)
NPIs that had fewer than 10 births2,439 (98 dropped)1,419,113 (dropped)
End: Final unique billing provider NPIs/header claims in the IP file included in the analysis2,439 (22%)1,419,113 (12%)
 

Defining Rural Hospitals: To define hospital rurality, this analysis uses 2020 USDA Rural-Urban Commuting Area (RUCA) Codes at the hospital zip code level, which is the main geographic identifier included in either the CMS Hospital Enrollments or AHA Annual Survey data. This analysis categorized hospitals as urban, rural adjacent, and remote rural as follows:

Urban

  • 1: Metropolitan core: primary flow is within a metro urban area (UA)
  • 2: Metropolitan high commuting: primary flow is 30% or more to a metro UA
  • 3: Metropolitan low commuting: primary flow is 10% to 30% to a metro UA

Rural adjacent

  • 4: Micropolitan core: primary flow is within an urban area of 10,000 to 49,999 people (micro UA)
  • 5: Micropolitan high commuting: primary flow is 30% or more to a micro UA
  • 6: Micropolitan low commuting: primary flow is 10% to 30% to a micro UA
  • 7: Small town core: primary flow is within an urban area of 9,999 or fewer people (small town UA)
  • 8: Small town high commuting: primary flow is 30% or more to a small town UA
  • 9: Small town low commuting: primary flow is 10% to 30% to a small town UA

Remote rural

  • 10: Rural area: primary flow is to a tract outside an UA

Calculating Distance Measures Between Hospitals: Hospital addresses were geocoded using data from OpenStreetMap (OSM). Hospital names and addresses were matched to OSM features, and corresponding latitude and longitude coordinates were extracted. Thirty-five hospitals (1%) were not matched to coordinates using OSM and were manually geocoded using Google Maps searches of hospital names and addresses.

Hospital distances were calculated between hospitals within the same state because most Medicaid enrollees obtain medical services within their state of residence, and because states have special processes for enrolling and paying out-of-state hospitals. Only 7% of hospitals in this analysis have the nearest hospital in another state, and results were not meaningfully changed by this decision.

To identify the nearest hospital within a state, straight-line distances were calculated using the Haversine formula (“as the crow flies”) for each hospital pair in a state, which is consistent with other hospital distance analyses. The hospital with the shortest “as the crow flies” distance was chosen as the nearest hospital. Travel mileage and times to the nearest hospital were then computed using the OSM road network via the Open Source Routing Machine (OSRM) public API. Routing followed drivable paths and incorporated road characteristics from OSM (see OSM Routing documentation).

The Status of Abortion-related State Ballot Initiatives Since Dobbs

Last updated on August 21, 2026

Since the Supreme Court’s Dobbs decision, overturning Roe v. Wade, voters in 17 states have weighed in on ballot measures regarding abortion– some more than once. In November 2026, voters in Idaho, Missouri, Nevada, and Virginia will weigh in on abortion measures that could change the legal status of abortion in their state. In addition, a measure in Colorado is in the process of collecting signatures.  

In 2024, 10 states voted on abortion measures that sought to affirm that the state constitution protects the right to abortion. Nebraska voted on two measures: one seeking to protect abortion and the other seeking to ban abortion after the first trimester. Measures protecting abortion rights succeeded in 7 states — Arizona, Colorado, Maryland, Missouri, Montana, Nevada, and New York — and failed in 3 — Florida, Nebraska, and South Dakota. Voters passed a measure amending the Nebraska state constitution prohibiting abortions after the first trimester.  

Prior to the 2024 election, the side favoring access to abortion prevailed in every state that voted on abortion-related ballot measures. In 2022 and 2023, California, Michigan, Ohio, and Vermont voters passed measures amending the state constitution to protect the right to abortion. Measures seeking to curtail the right to abortion in Kentucky, Kansas, and Montana failed.  

There are two ways a measure may be placed on the ballot: through citizen initiative or legislative referral. 

  • Legislatively-referred  measures are introduced and approved by lawmakers before they appear on the ballot for citizens to vote on. 
  • Citizen-initiated  measures are written by citizen groups and are placed on the ballot if they receive enough signatures.  

Not all states allow for citizen-initiated ballot measures. For more background information on abortion related ballot initiatives, please see our brief Addressing Abortion Access through State Ballot Initiatives

For more information on confirmed and potential abortion-related ballot measures in the 2026 election, please see our brief Abortion on the 2026 Ballot: The Evolving Landscape of State Abortion Initiatives

Status of Abortion-Related Ballot Measures Since Dobbs, as of August 21, 2026 (Table)