Hospital Margins Rebounded in 2023, But Rural Hospitals and Those With High Medicaid Shares Were Struggling More Than Others

Authors: Zachary Levinson, Jamie Godwin, and Tricia Neuman
Published: Dec 18, 2024

Hospitals account for 30% of total health care spending—$1.4 trillion in 2022—with expenditures projected to rise rapidly through 2032, contributing to higher costs for families, employers, Medicare, Medicaid, and other public payers. Policymakers have sought to reduce spending on hospital care as part of a broader effort to make health care more affordable and reduce the federal deficit. In recent years, for example, there has been bipartisan interest in site-neutral payment reforms, which would reduce Medicare program and beneficiary spending by aligning Medicare rates for certain outpatient services across care settings. The next Trump administration and Republicans in Congress may also seek to cut Medicaid spending, which could result in fewer dollars flowing to hospitals.

At the same time, there are ongoing questions about the effects of policies that reduce spending on hospital finances and access to care, with particular attention to the implications for rural and safety-net hospitals. For example, Senators Cassidy and Hassan recently released a framework for site-neutral payment reforms that would reinvest savings into rural and high-needs hospitals.

This analysis examines hospital margins for non-federal general short-term hospitals in the U.S from 2018 through 2023, the most recent year with virtually complete cost report data. The analysis is based on RAND Hospital Data, a cleaned version of Medicare cost reports. Total margins are defined as net income (revenues minus expenses) divided by revenues. This analysis focuses on operating margins (instead of total margins) to examine the extent to which hospitals profited or lost money on patient care and other operating activities, rather than on other sources, such as investments. Operating margins are approximated using the same calculation as for total margins after subtracting reported investment income and charitable contributions from revenues. Results for groups of hospitals reflect aggregate margins based on total relevant revenues and expenses, which is equivalent to the average margin after weighting hospitals by their revenue. A number of datasets provide information about hospital finances, though each has limitations, and cost reports are no exception. See Methods for additional information.

Key Takeaways

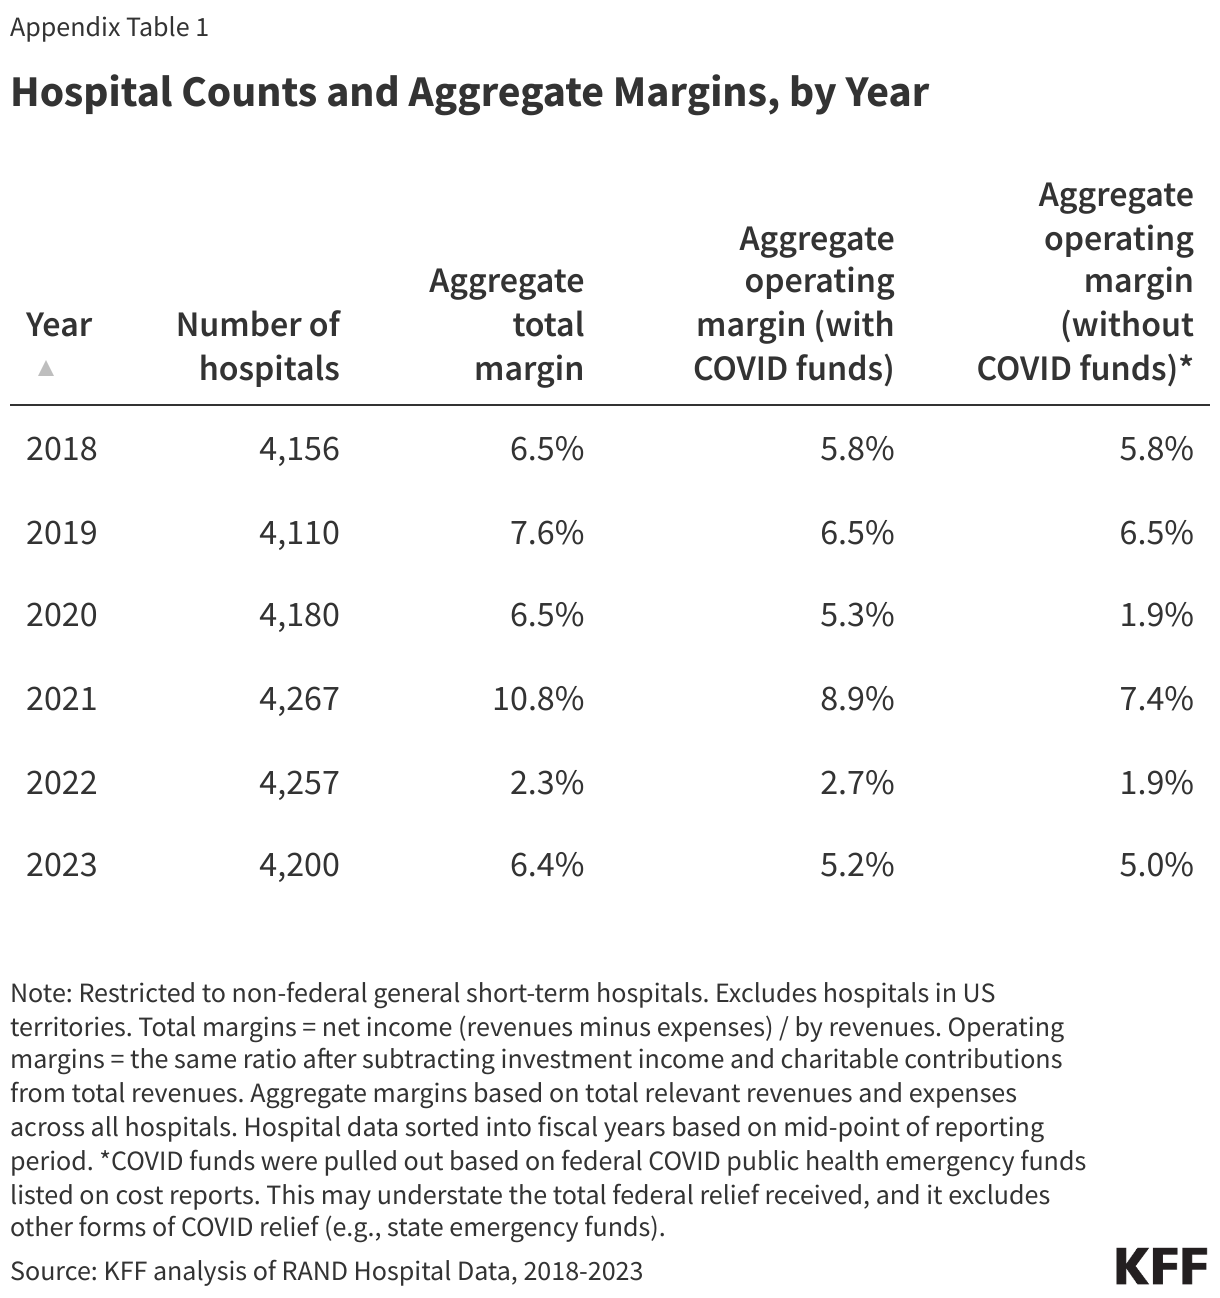
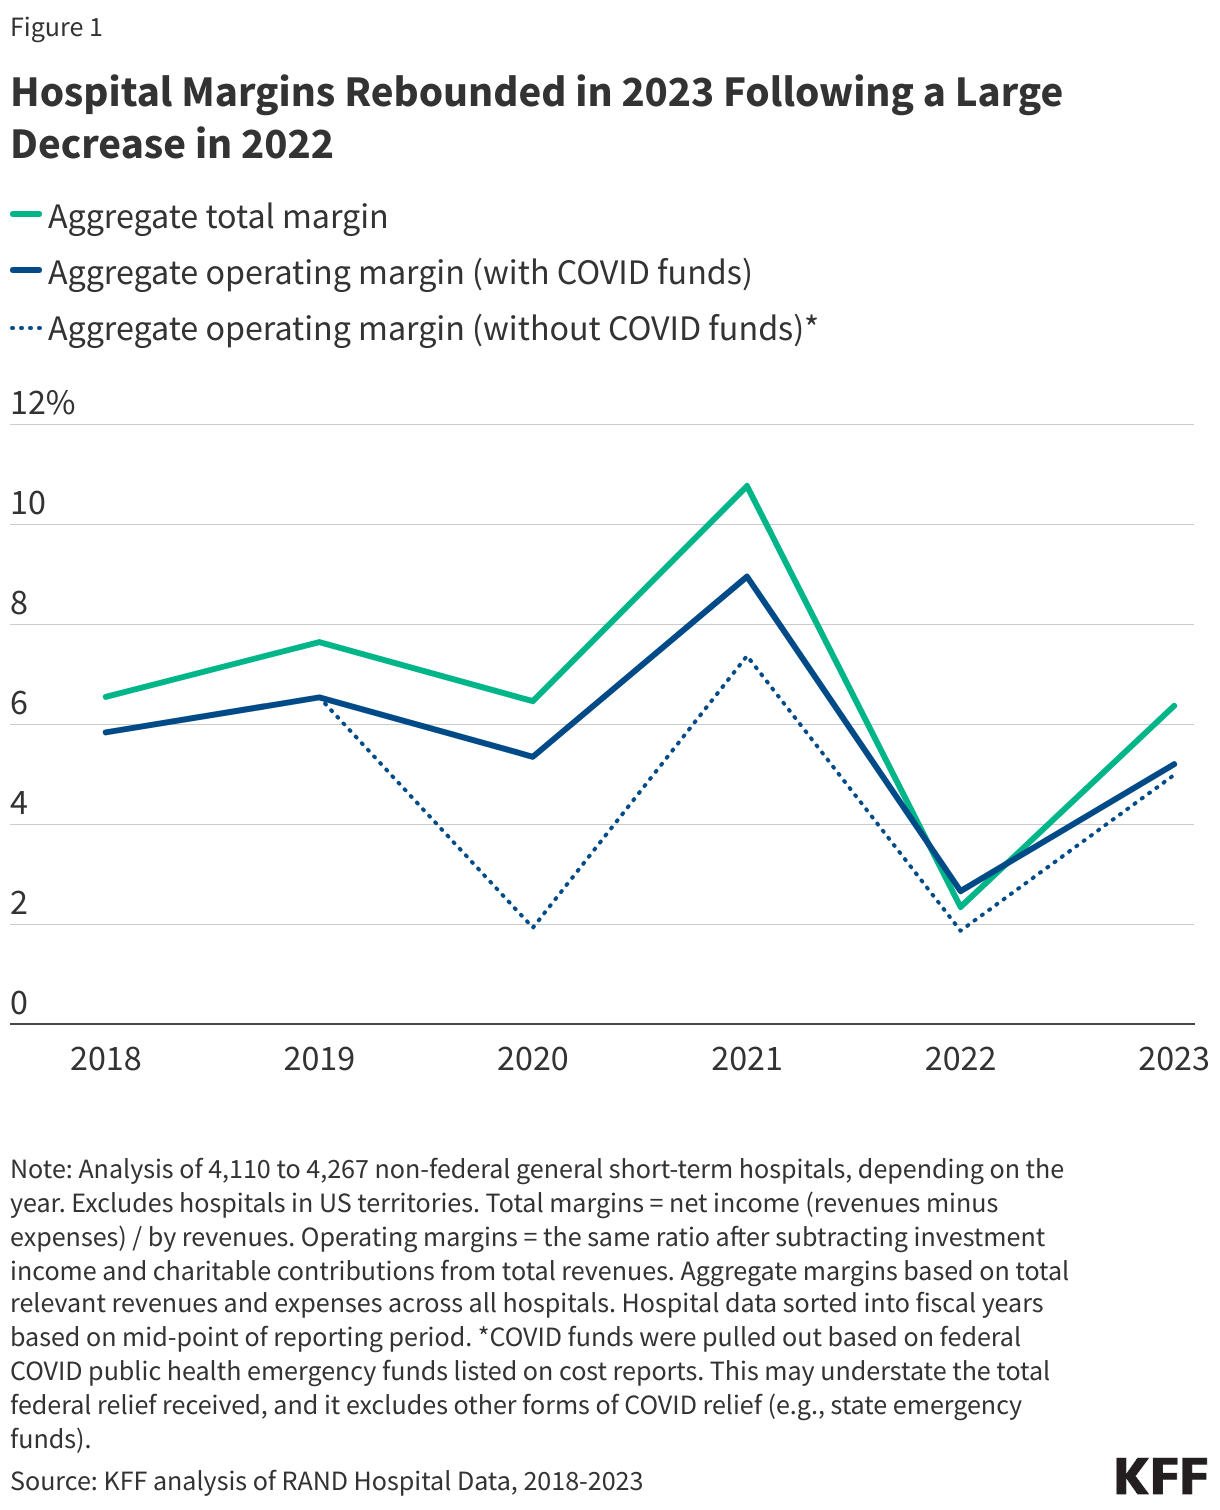
  • Aggregate hospital margins rebounded in 2023 following a large decrease in 2022. This is true for operating margins, which decreased from 8.9% in 2021 to 2.7% in 2022 before increasing to 5.2% in 2023. It is also true for total margins, which decreased from 10.8% in 2021 to 2.3% in 2022 before increasing to 6.4% in 2023. However, both aggregate operating margins and total margins remained below 2019 pre-pandemic levels in 2023.
  • Aggregate operating margins were positive in 2023 (5.2%), but about two in five hospitals (39%) had negative margins in that year. About one in five (22%) had operating margins less than -5%.
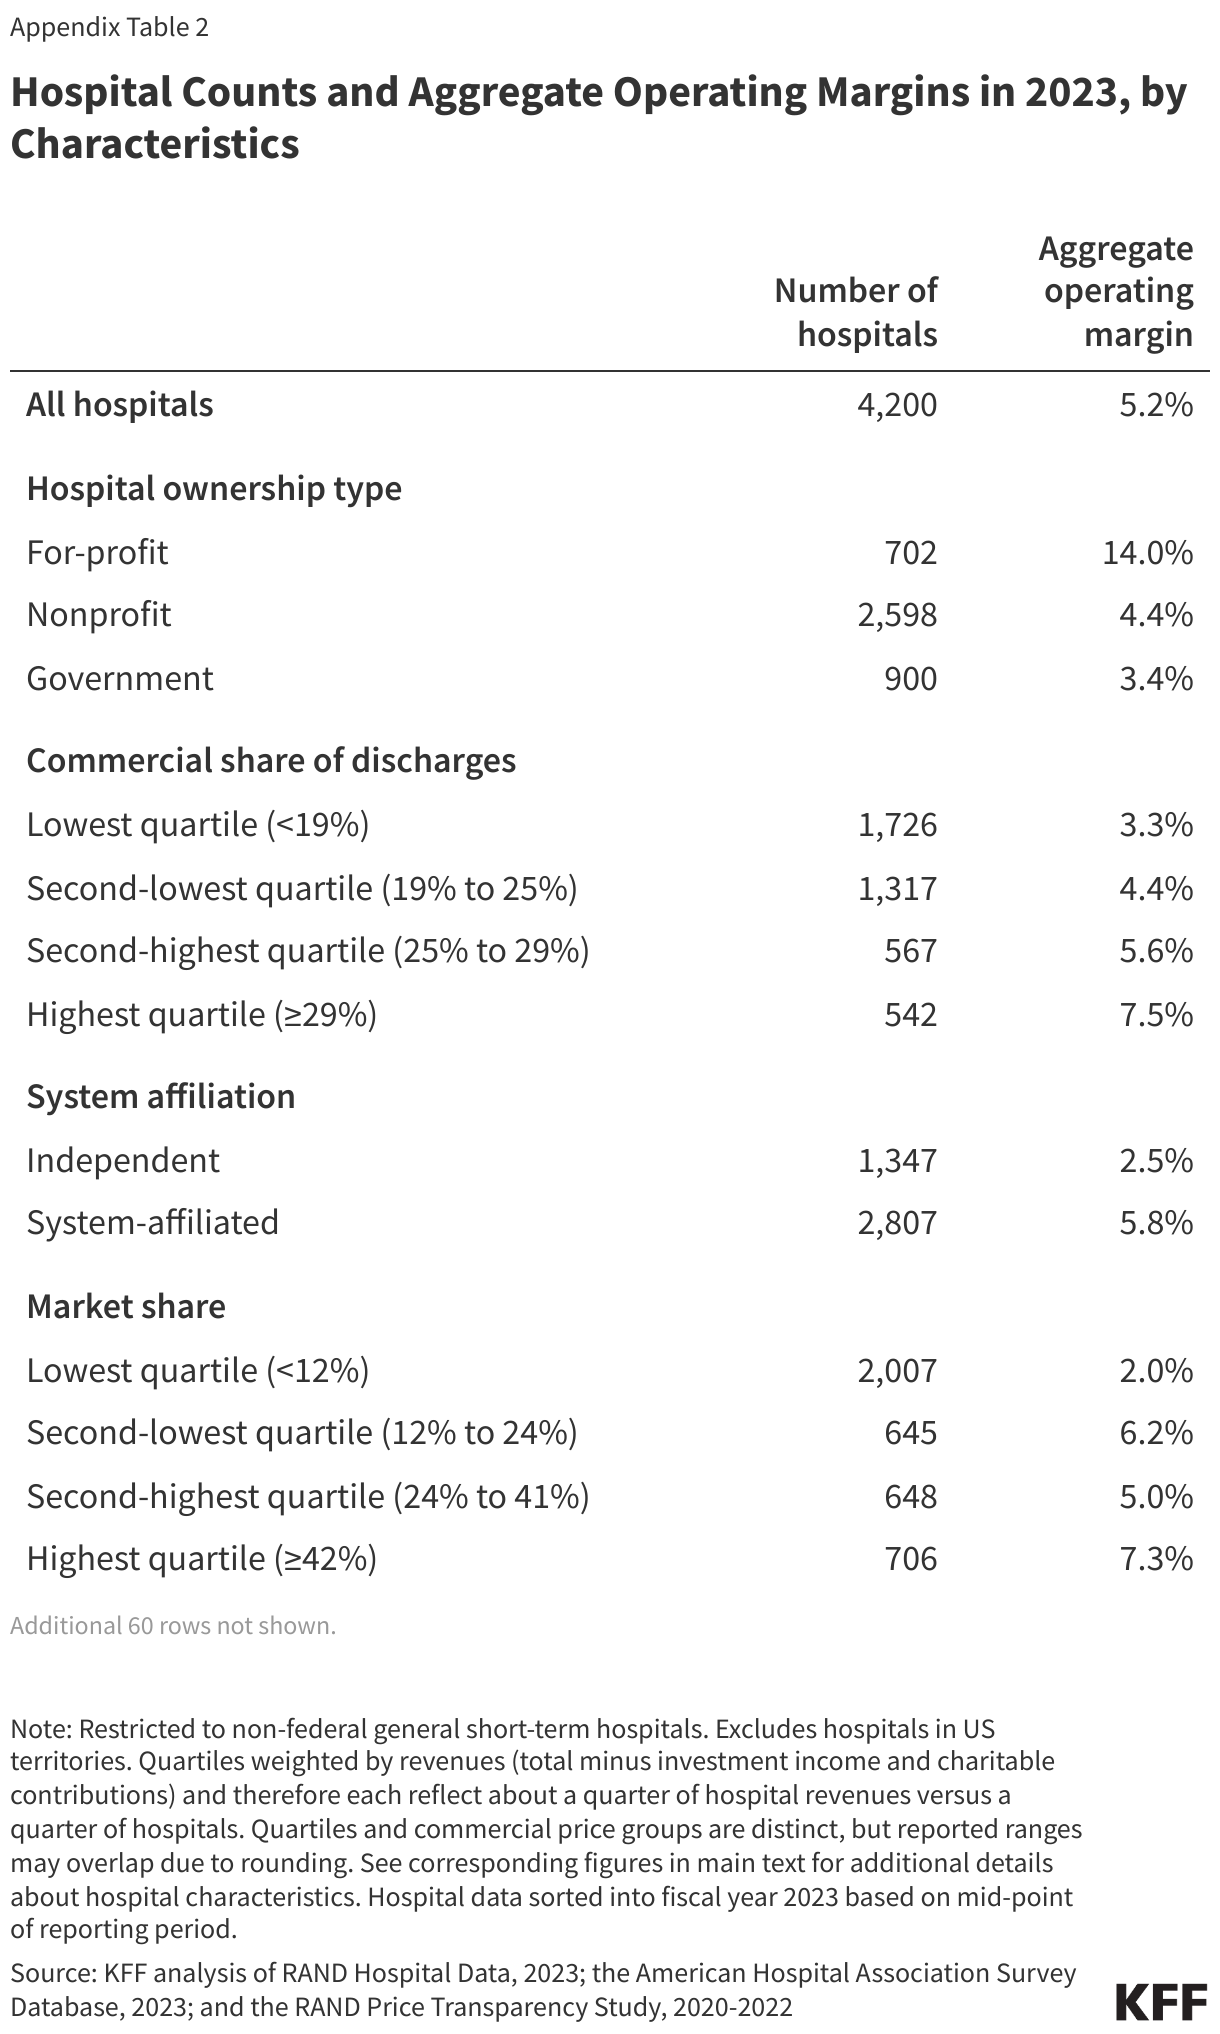
  • Operating margins were higher than average among for-profit hospitals, hospitals with a high share of commercial discharges, and system-affiliated hospitals in 2023. For-profit hospitals had higher operating margins than nonprofit and government hospitals (14.0% versus 4.4% and 3.4%, respectively). Hospitals with a relatively high commercial share of total discharges had higher operating margins than hospitals with low shares (7.5% versus 3.3% among the top versus bottom quarter based on commercial share, respectively) (quartiles are weighted by revenues throughout). System-affiliated hospitals had higher operating margins than independent hospitals (5.8% versus 2.5%).
  • Operating margins in 2023 were also higher than average among hospitals with relatively high commercial prices. Operating margins were relatively high among hospitals with commercial prices that were greater than 300% of Medicare rates, especially among hospitals with high commercial shares. In contrast, operating margins were relatively low among hospitals with high Medicaid shares (see below).
  • Operating margins were lower than average among hospitals with high Medicaid shares, which was true in both rural and urban areas. Operating margins were lower among hospitals with a relatively high Medicaid share (2.3% among the top quarter of hospitals based on Medicaid shares versus 7.0% among the bottom quarter). Operating margins were relatively low for hospitals with high Medicaid shares in both rural and urban areas (1.7% and 2.3%, respectively).
  • Operating margins were lower than average among rural hospitals in 2023. Operating margins were lower among hospitals in rural than urban areas (3.1% versus 5.4%, respectively) and were especially low among hospitals in rural areas that were not micropolitan areas (1.8%), i.e., that did not include and were not closely connected to any substantial population nucleus. However, operating margins were higher among for-profit than nonprofit rural hospitals (8.5% versus 3.5%, respectively). Operating margins were also lower among hospitals with Medicare rural designations, particularly among low-volume hospitals and Medicare dependent hospitals (1.7% and 1.8%, respectively).

Aggregate Hospital Margins Rebounded in 2023 Following a Large Decrease in 2022

Aggregate operating margins decreased from 8.9% in 2021 to 2.7% in 2022 before increasing to 5.2% in 2023 (Figure 1). Similarly, aggregate total margins decreased from 10.8% in 2021 to 2.3% in 2022 before increasing to 6.4% in 2023. While operating and total margins both increased in 2023, they remained below 2019 pre-pandemic levels (6.5% for operating margins and 7.6% for total margins). Operating margins were at a record high in 2021 for hospitals reimbursed under the inpatient prospective payment system (IPPS) but were lower in 2022 than they had been since 2008—i.e., during the Great Recession—according to related analyses from the Medicare Payment and Advisory Commission.

Decreases in operating margins in 2022 were likely due to the erosion of COVID funds, costs associated with labor shortages, and increased supply expenses due to high inflation rates, among other factors. Improvements in 2023 may have been due a number of factors, including stabilizing labor expenses, decreases in average length of stay, and increases in revenue.
Hospital Margins Rebounded in 2023 Following a Large Decrease in 2022

Some of the major credit rating agencies have reported relatively stable operating margins among rated not-for-profit health systems from 2022 to 2023 and have projected gradual improvements over time. These trends may differ from the main analysis here because, among other factors, they look at not-for-profit systems and report median (rather than aggregate or weighted average) operating margins. Industry reports, based on a non-representative sample of hospitals, indicate that finances have improved through October 2024 relative to 2022.

Aggregate Operating Margins Were Positive in 2023, But About Two in Five Hospitals (39%) Had Negative Margins

While aggregate operating margins were positive in 2023 (5.2%), operating margins varied substantially across hospitals. On one end of the spectrum, about one in seven hospitals (15%) had relatively high operating margins of at least 15%, while about one in five (22%) had positive but relatively modest margins of less than 5%, including about one in ten (11%) with positive margins of less than 2.5% (not shown). Having positive but modest margins may signal financial challenges for hospitals.
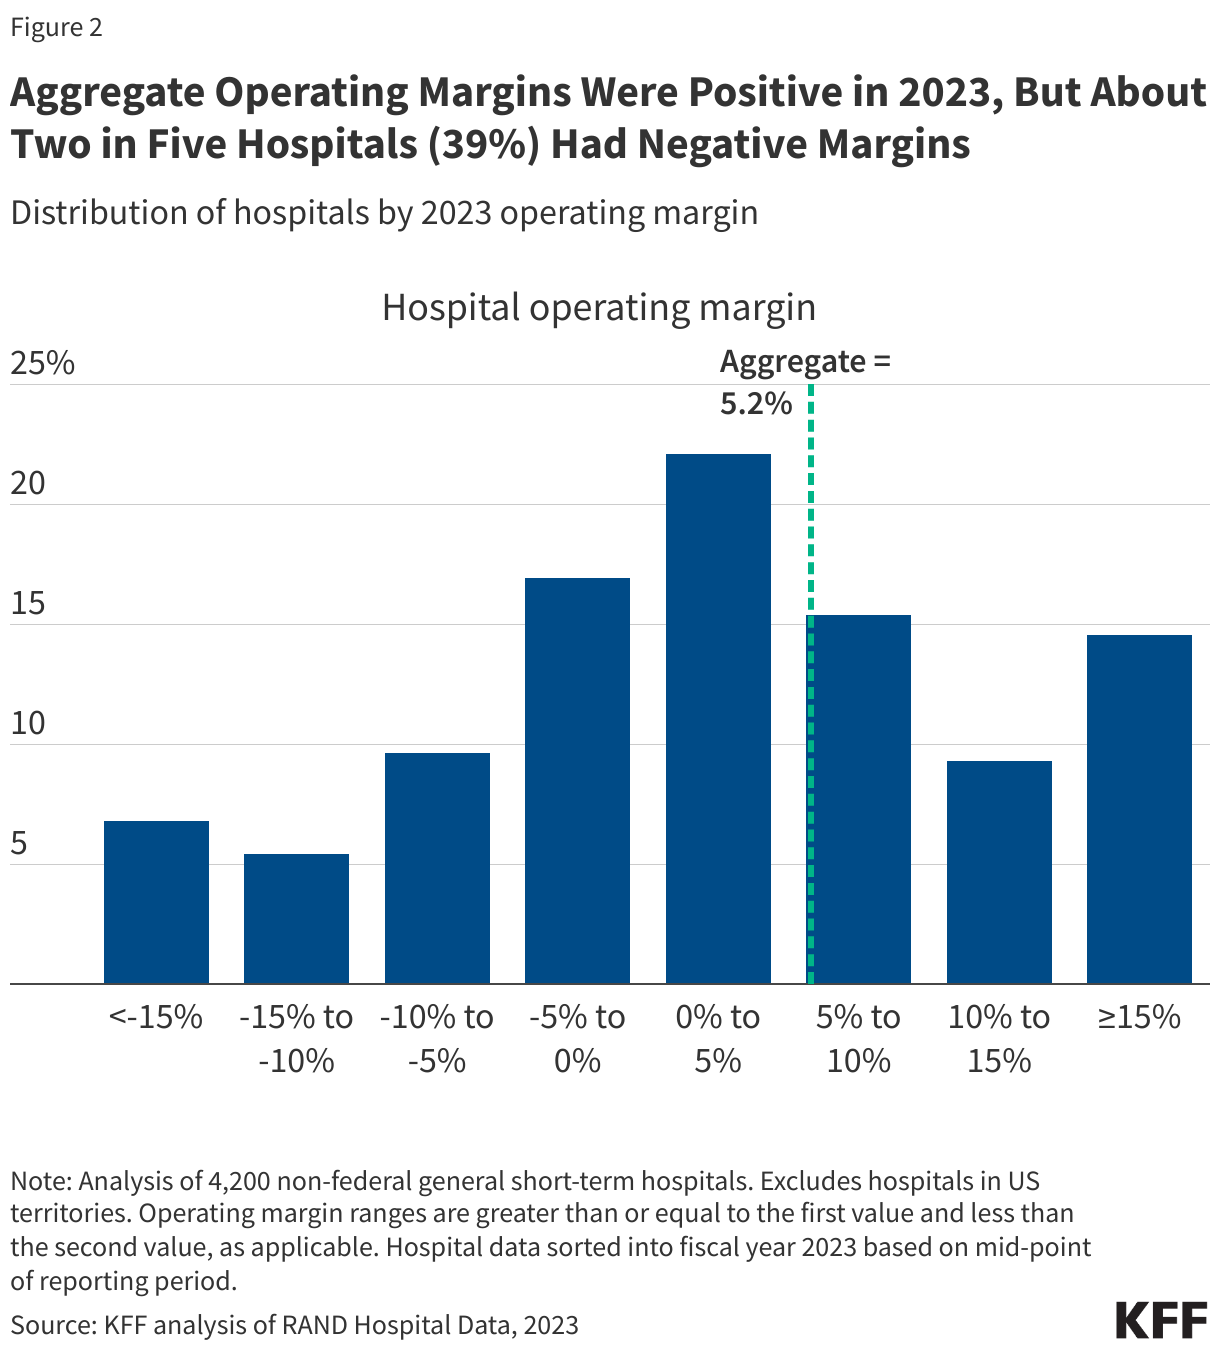
Aggregate Operating Margins Were Positive in 2023, But About Two in Five Hospitals (39%) Had Negative Margins

At the same time, about two in five hospitals (39%) had negative margins, and about one in five (22%) had margins of less than -5%. While some of these hospitals may be able to weather financial challenges for a period of time if they have sufficient days of cash on hand, those without sufficient days of cash on hand could be especially challenged to maintain current services or remain open. Based on a prior KFF analysis, the majority of nonprofit hospitals and health systems analyzed with negative operating margins had at least “strong” levels of days cash on hand in 2022, though that analysis was based on data that underrepresent entities likely to be more financially vulnerable.

Operating Margins Were Higher Than Average Among For-Profit Hospitals, Hospitals With High Commercial Discharge Shares, and System-Affiliated Hospitals and Were Lower Than Average Among Hospitals With Low Market Shares in 2023

For-profit hospitals—which accounted for 17% of facilities—had much higher operating margins than nonprofit and government hospitals (14.0% versus 4.4% and 3.4%, respectively) (see Figure 3). For-profit hospitals may have a greater motivation to operate more efficiently and engage in other strategic behaviors to increase their margins, such as focusing on relatively profitable services lines, dropping unprofitable service lines (like obstetrics), or locating in wealthier areas that have more residents with commercial insurance and fewer with public or no insurance. As is the case throughout this analysis, differences in operating margins across groups of hospitals could reflect a variety of factors.

Operating margins were also higher than average among hospitals where commercially-insured patients accounted for a relatively large share of discharges. For example, operating margins were 7.5% versus 3.3% when comparing hospitals in the top versus bottom quarter based on commercial shares (quartiles are weighted by revenues throughout). One factor that likely plays a role in these results is that commercial payers generally reimburse hospital care at higher rates than Medicare and Medicaid, the two other major payers. For instance, a KFF review found that commercial prices were nearly double Medicare rates for hospital services when averaging findings across studies, and one recent analysis found that commercial prices were 254% of Medicare rates for hospital services on average in 2022.

Operating margins were also higher among hospitals affiliated with a health system than independent hospitals (5.8% versus 2.5%). Higher operating margins among system-affiliated hospitals could reflect the effects of consolidation, among other factors. Consolidation might lead to higher margins, for example, to the extent that merging providers are able to reduce operating costs or—as suggested by a large body of evidence—charge higher prices by having greater market power.

Finally, operating margins were lower among hospitals that accounted for a relatively low share of hospital discharges in their market. For example, operating margins were 2.0% versus 7.3% when comparing the bottom versus top quarter of hospitals based on their market share (or the market share of the health system that they are a member of, as applicable). Hospitals with large market shares may be able to negotiate higher rates and, if part of a larger system, benefit from economies of scale, among other factors that could drive higher margins.
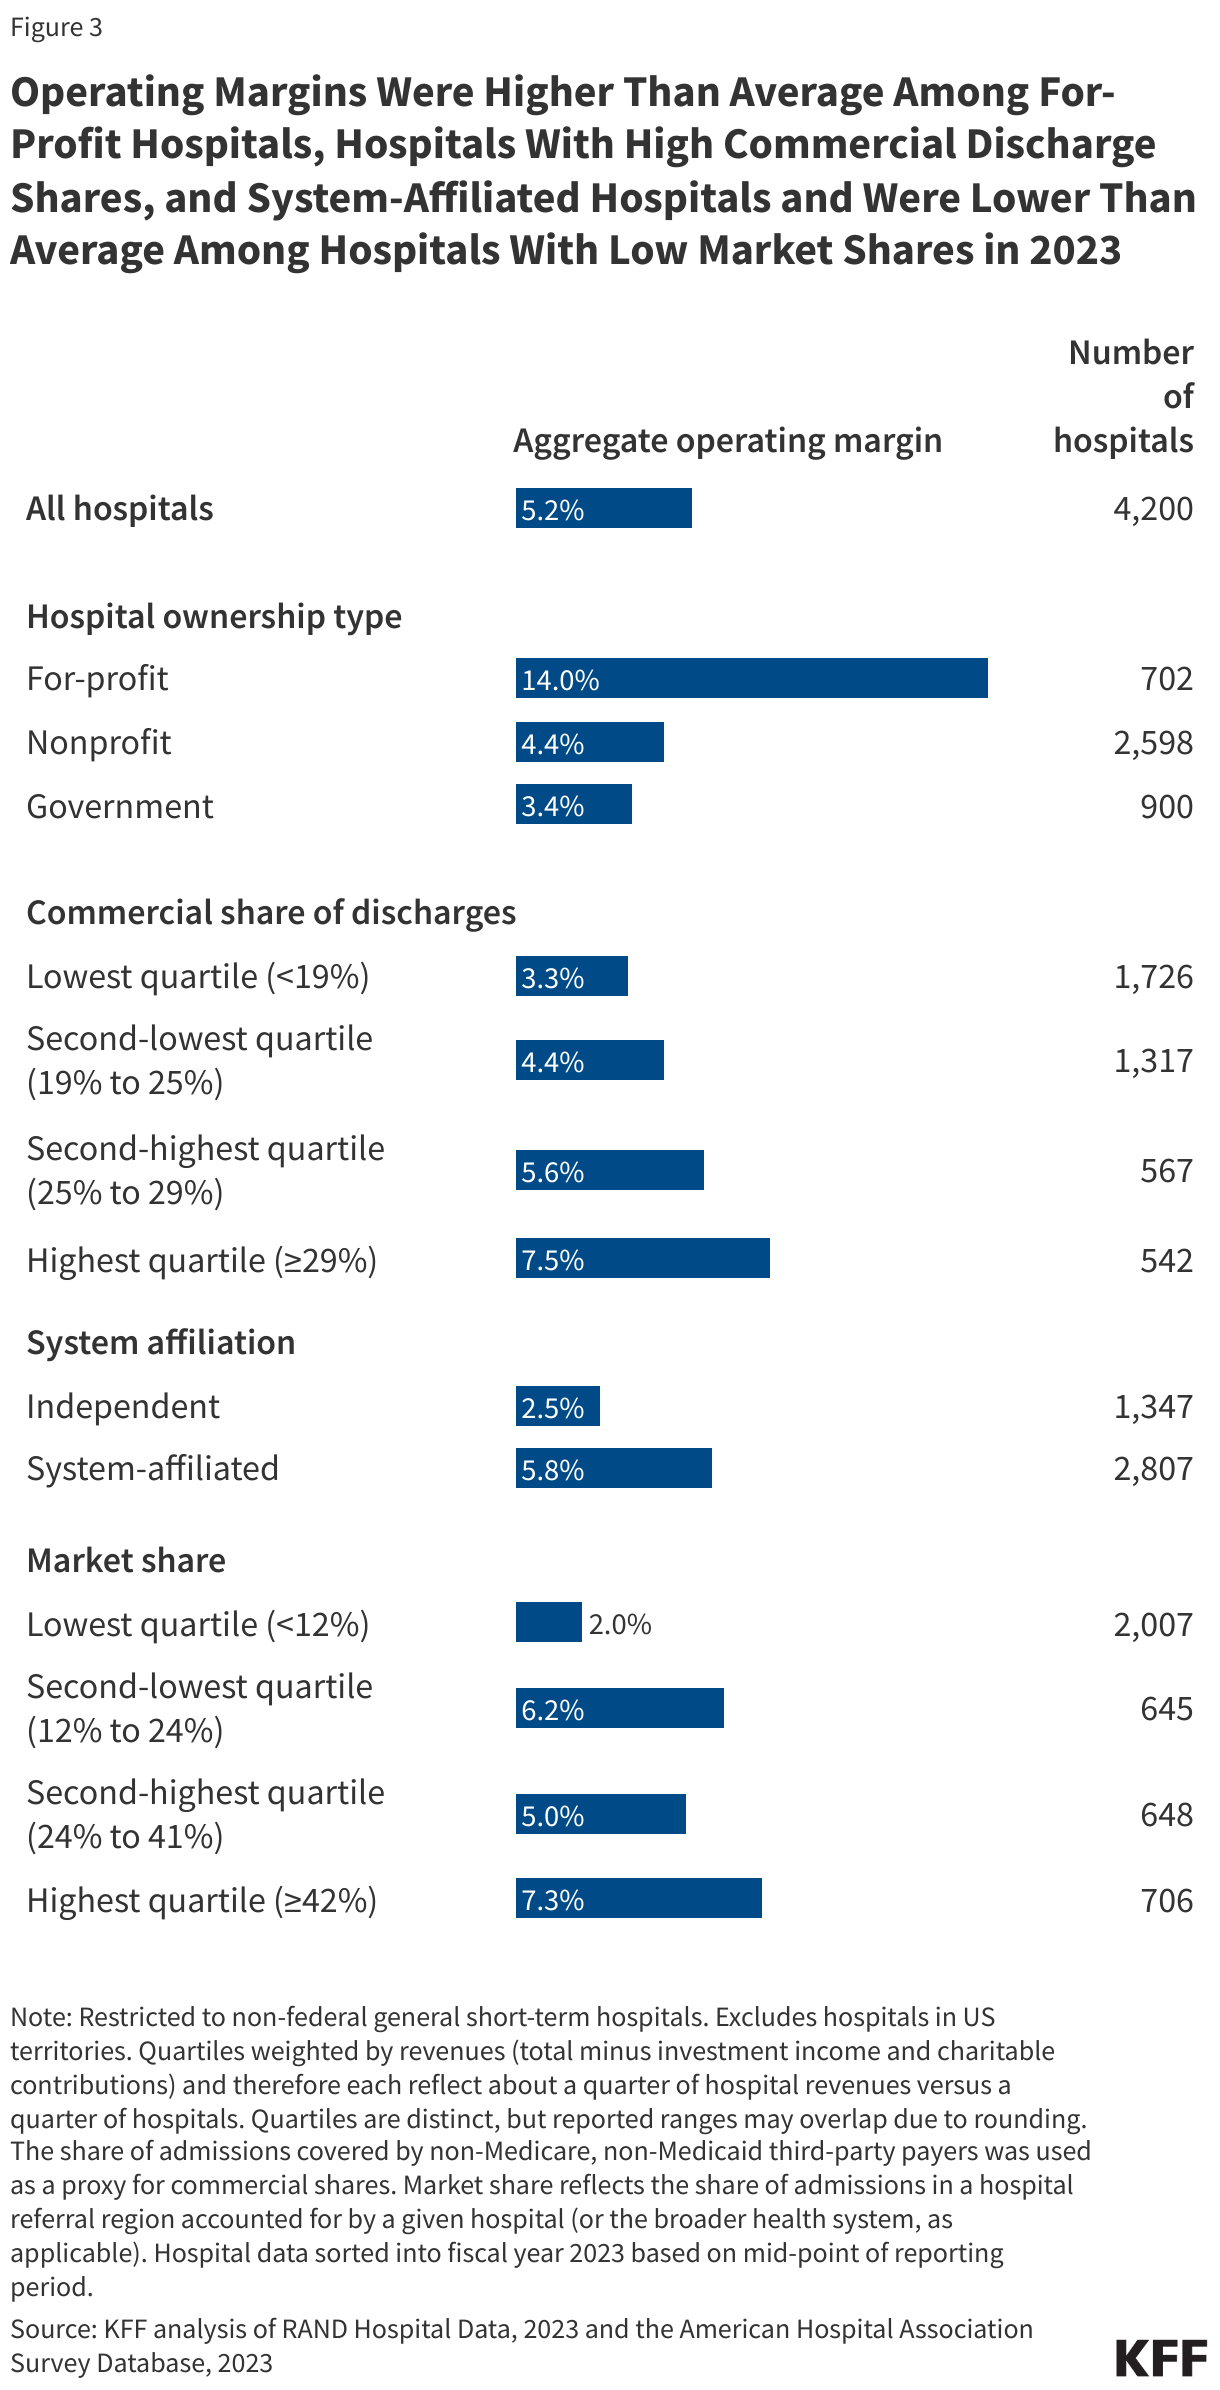
Operating Margins Were Higher Than Average Among For-Profit Hospitals, Hospitals With High Commercial Discharge Shares, and System-Affiliated Hospitals and Were Lower Than Average Among Hospitals With Low Market Shares in 2023

Operating Margins in 2023 Were Higher Than Average Among Hospitals With High Prices, Especially Among Those With a Relatively High Commercial Shares

Operating margins were relatively high among hospitals with commercial prices that were greater than 300% of Medicare rates (8.9%) and were even higher (10.5%) among those with a relatively high commercial share of total discharges (i.e., with at least a 25% commercial share) (see Figure 4). In contrast, operating margins were relatively low among hospitals with commercial prices below 200% of Medicare rates (1.0%) and were even lower (0.8%) among those with low commercial patient shares. This aligns with an analysis from researchers at the Urban Institute and Harvard that found that high commercial prices were associated with higher operating margins and more days of cash on hand.

Policymakers have explored a number of options to rein in commercial prices. This analysis suggests that hospitals with the highest prices and largest commercial shares as a group are in a better position to absorb any restraints on prices, though the impact would vary across hospitals.
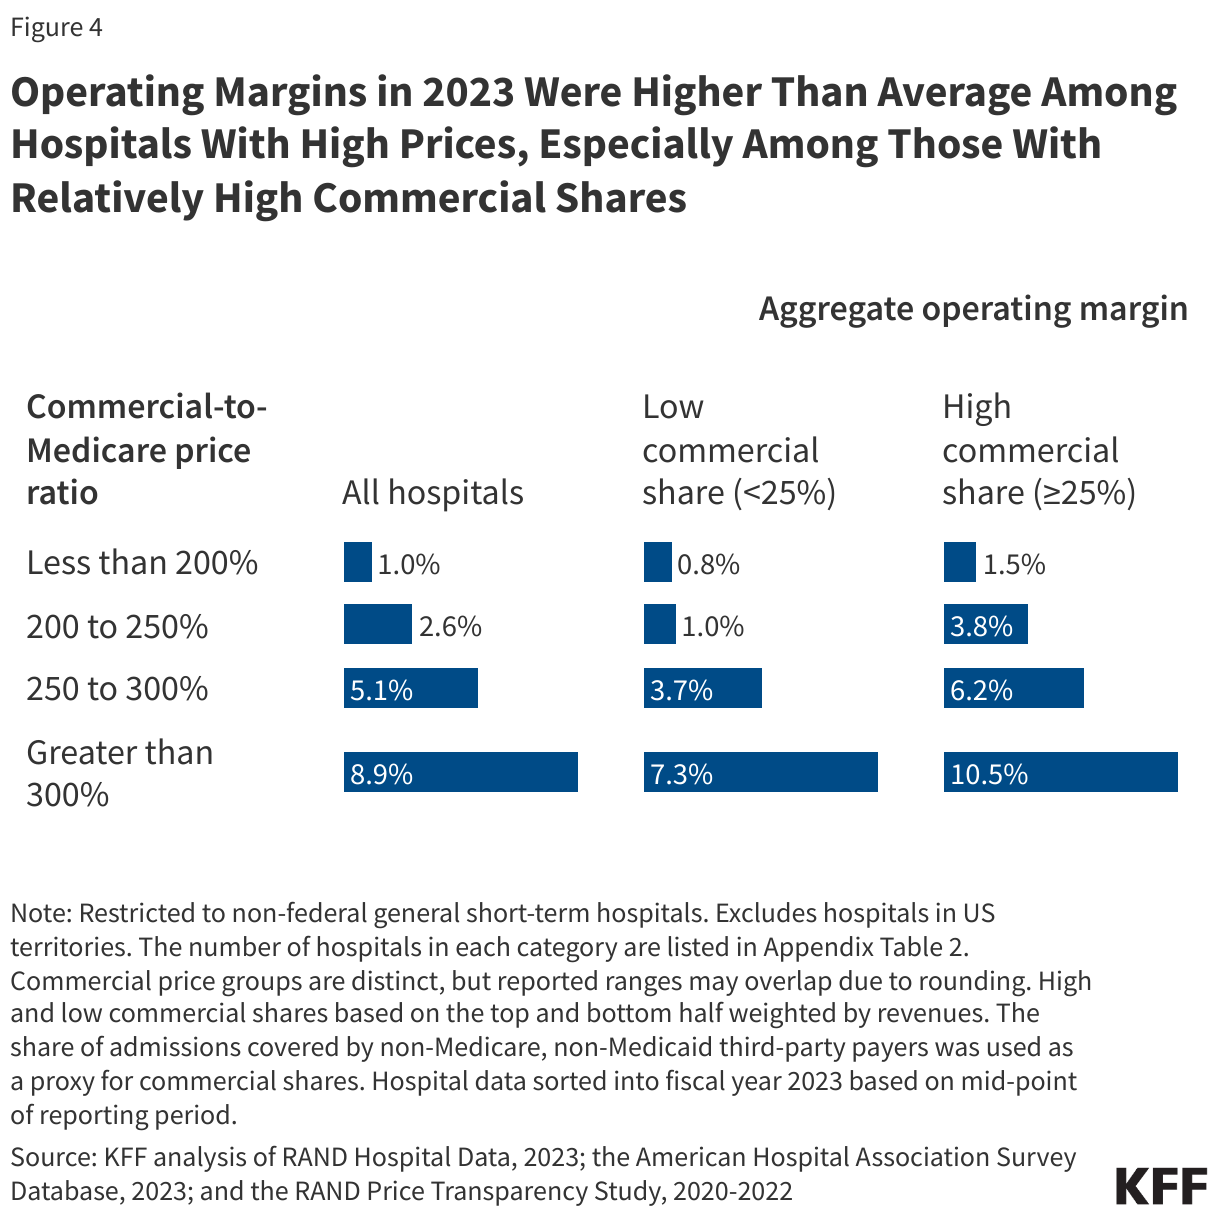
Operating Margins in 2023 Were Higher Than Average Among Hospitals With High Prices, Especially Among Those With Relatively High Commercial Shares

While Operating Margins Were Higher Than Average Among Hospitals With High Commercial Shares in 2023, They Were Lower Than Average Among Hospitals With High Medicaid Shares, Which Was True in Both Urban and Rural Areas

Hospitals with high commercial shares had relatively high operating margins (e.g., 7.5% versus 3.3% when comparing the top versus bottom quarter of hospitals weighted by revenues based on commercial share) (see Figure 3 above) while hospitals with high Medicaid shares had relatively low operating margins (e.g., 2.3% versus 7.0% when comparing the top versus bottom quarter of hospitals weighted by revenues based on Medicaid share) (see Figure 5).

Operating margins in 2023 were relatively low among hospitals with high Medicaid shares in both rural and urban areas (1.7% and 2.3%, respectively) (see Figure 5). In comparison, the operating margin among all hospitals was 5.2% in 2023. While operating margins were lower among hospitals in rural than urban areas overall (3.1% versus 5.4%, respectively) (see Figure 7 below), hospitals with high Medicaid shares in urban areas stand out as another example of hospitals that were struggling more than others.

Some policymakers are especially attentive to the financial stability of safety-net hospitals given their role in providing access to patients with limited resources and other sources of vulnerability. The share of patients covered by Medicaid may signal the extent to which a given hospital cares for a disproportionate share of low-income patients (see Methods for more detail).
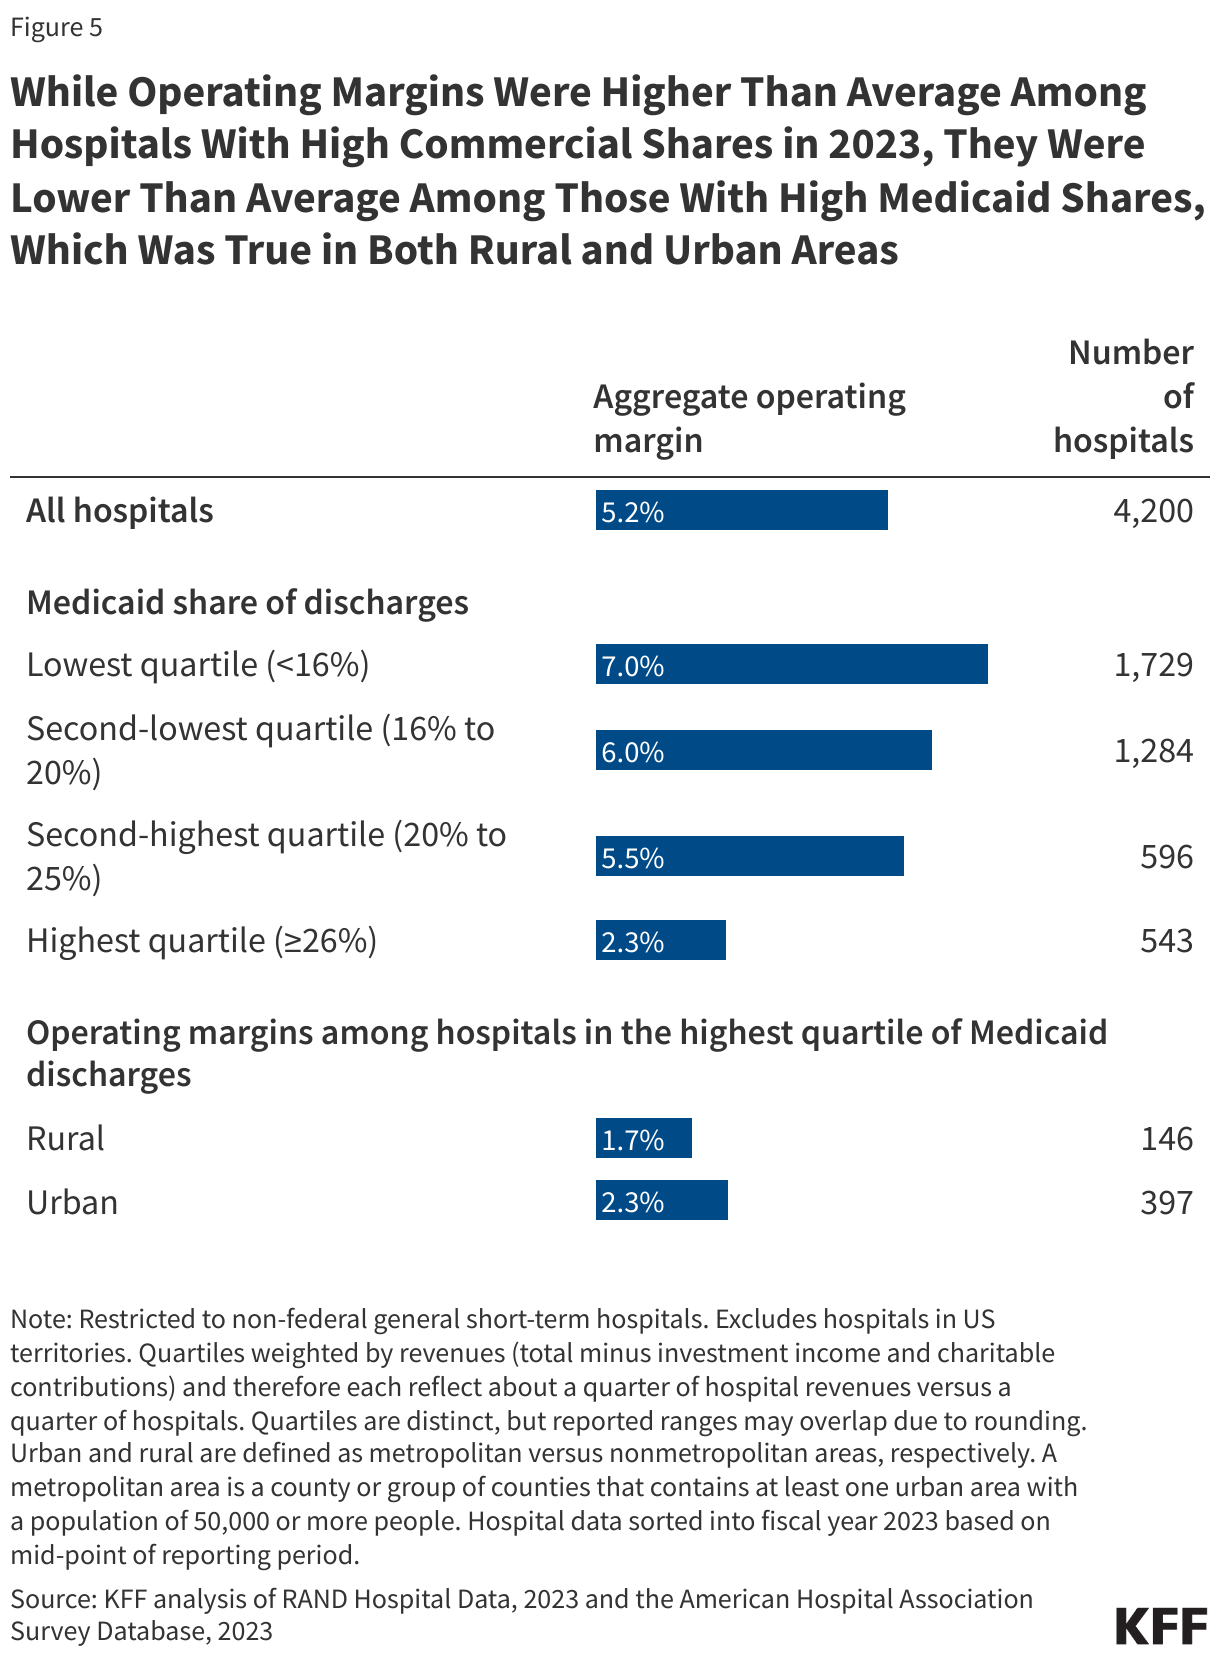
While Operating Margins Were Higher Than Average Among Hospitals With High Commercial Shares in 2023, They Were Lower Than Average Among Those With High Medicaid Shares, Which Was True in Both Rural and Urban Areas

Operating Margins Were Also Lower Than Average Among Hospitals With High Medicare Shares in 2023

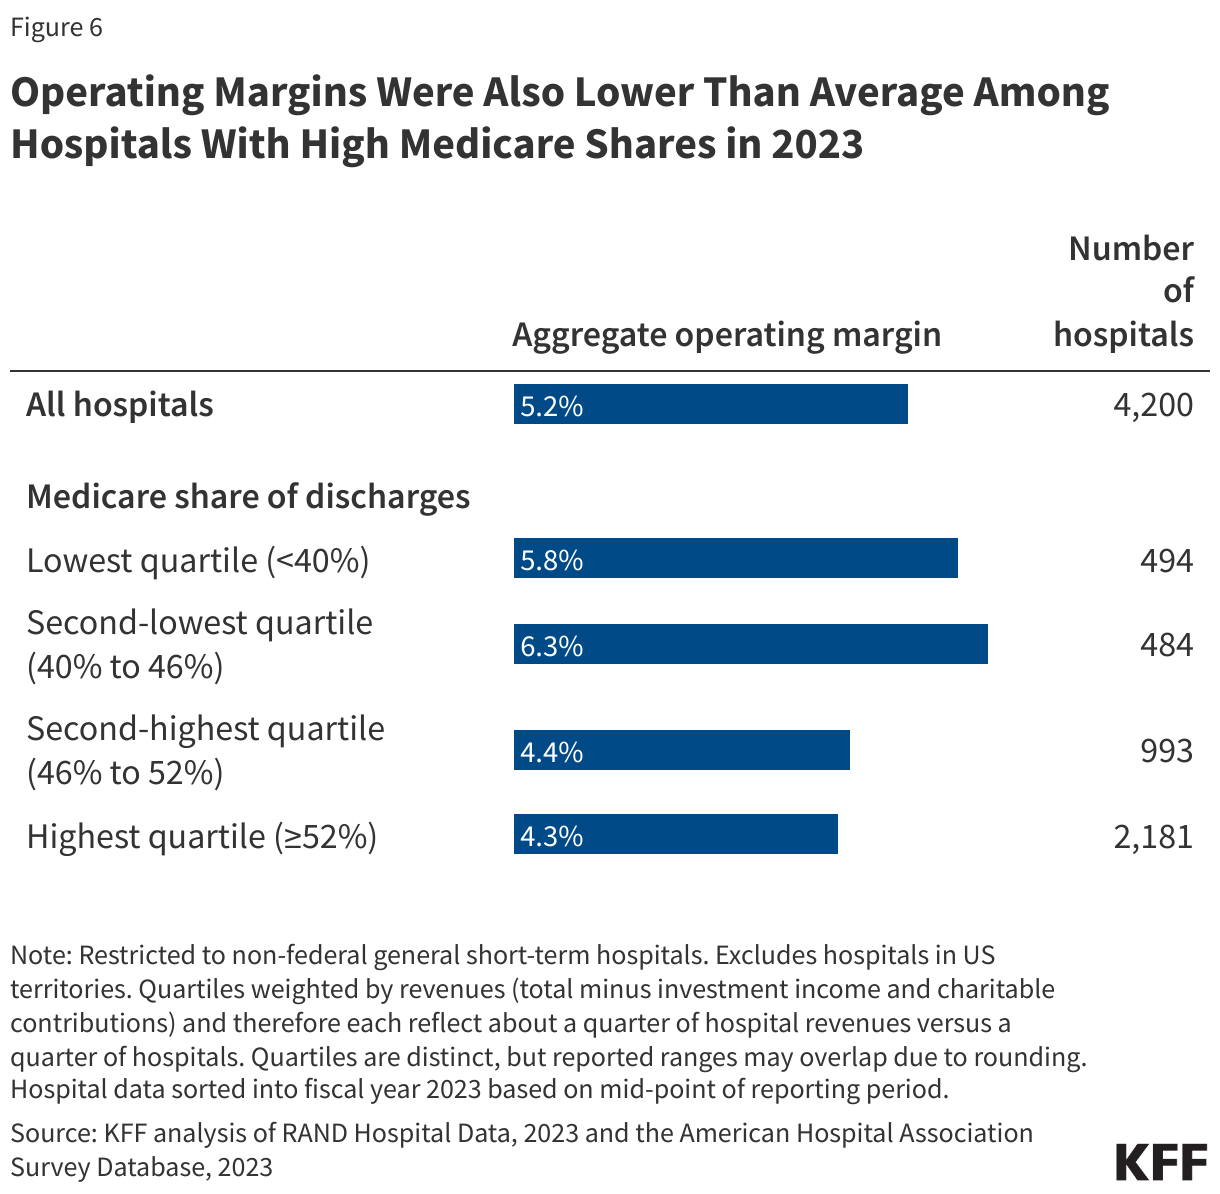
Operating margins were 4.3% in 2023 among hospitals in the top quarter based on Medicare share of discharges compared to 5.8% among hospitals in the bottom quarter (see Figure 6). Part of this difference may reflect the fact that hospitals with high Medicare shares were more likely to be in rural areas (54% of hospitals in the top quarter of Medicare shares were in rural areas versus 23% of the hospitals in the bottom quarter). As described below, rural hospitals had lower than average operating margins in 2023.

While operating margins among hospitals in the top quarter of Medicare shares were lower than among hospitals overall, they were higher relative to hospitals in the top quarter of Medicaid shares (4.3% versus 2.3%, respectively).
Operating Margins Were Also Lower Than Average Among Hospitals With High Medicare Shares in 2023

Operating Margins Were Lower Than Average Among Rural Hospitals in 2023

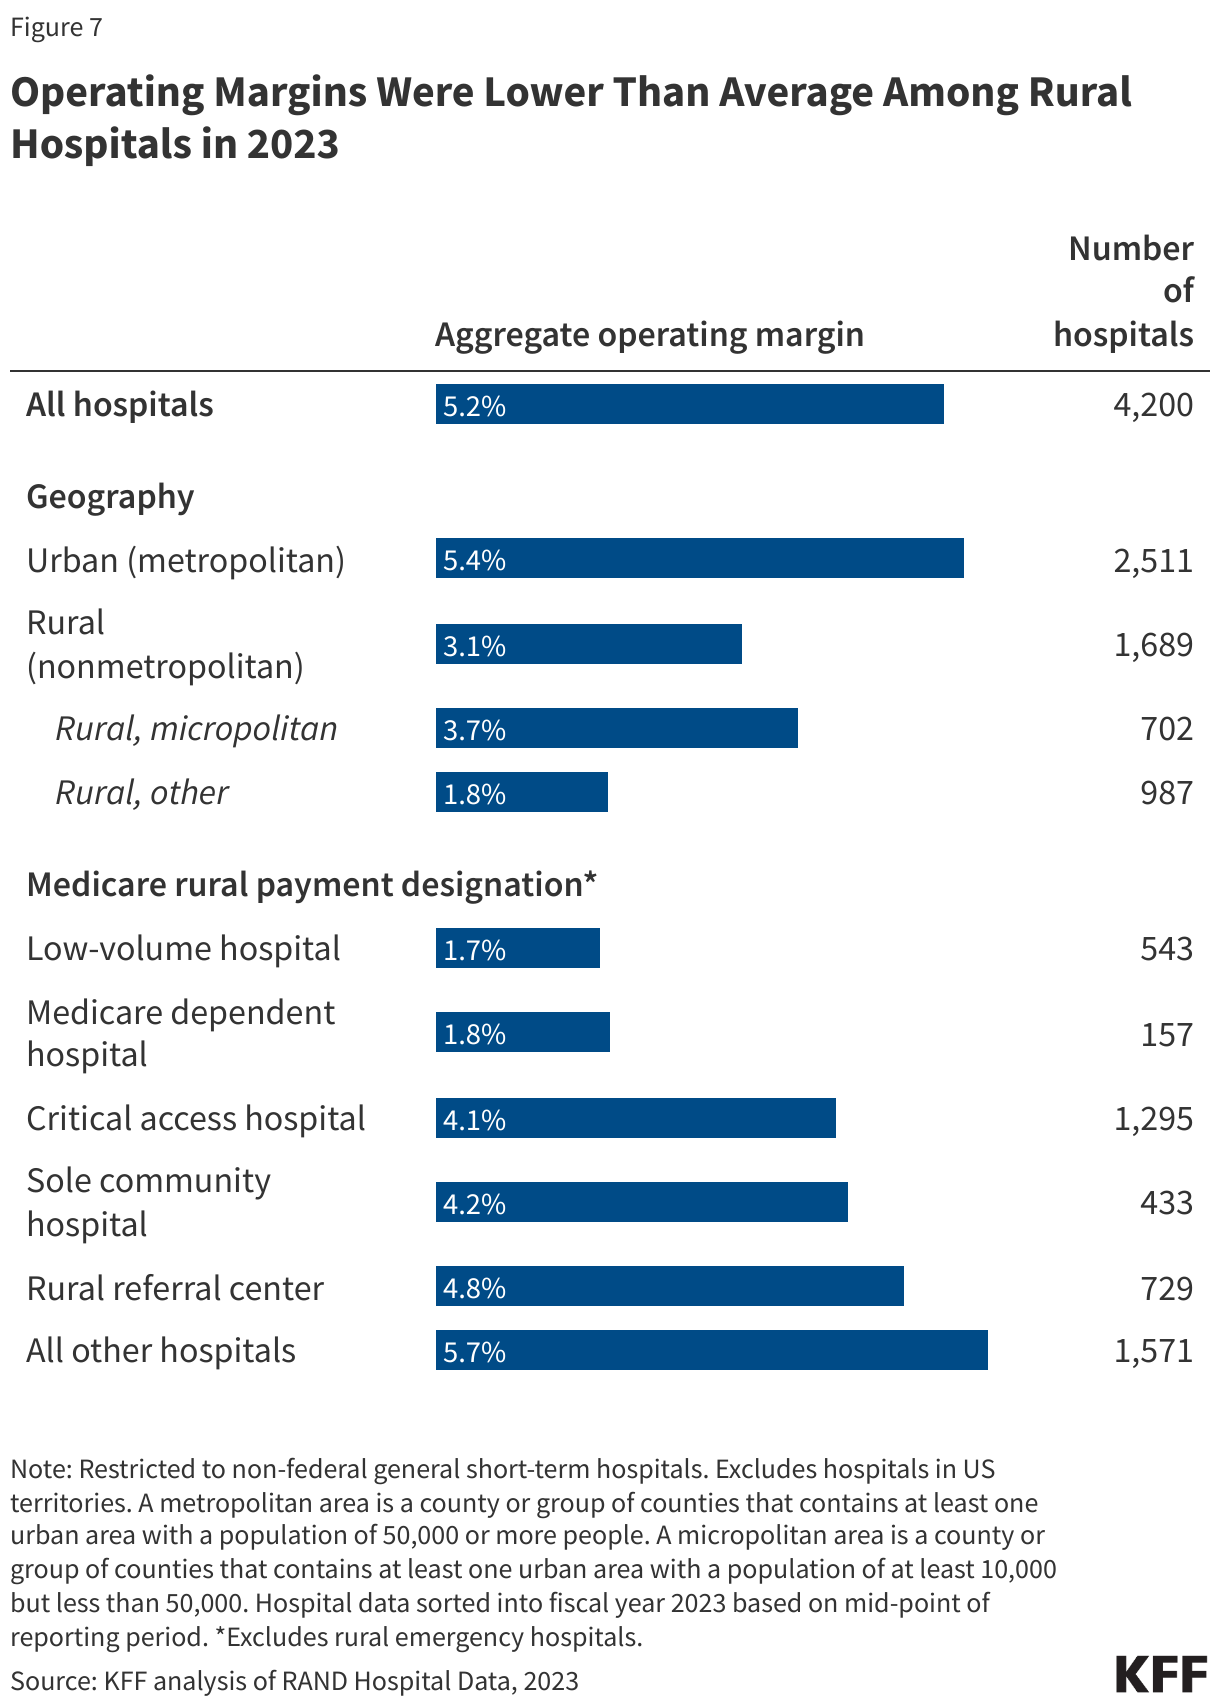
Operating margins were lower among hospitals in rural versus urban (nonmetropolitan versus metropolitan) areas (3.1% versus 5.4%, respectively) and were especially low among hospitals in rural areas that were not micropolitan areas (1.8%) (Figure 7), i.e., that did not include and were not closely connected to any substantial population nucleus (see Methods for more about urban and rural definitions). While 48 states in this analysis had at least one rural hospital, rural hospitals were distributed unevenly across the country. For example, a quarter of rural hospitals were located in Iowa, Kansas, Minnesota, Nebraska, or Texas. Rural hospitals often face unique financial challenges, such as low patient volume, which may lead to higher costs on average and limit the ability to offer specialized services.

Operating margins varied across rural hospitals in 2023, as was the case when looking at hospitals overall. For example, more than four in ten (44%) rural hospitals had negative operating margins while more than half (56%) had positive operating margins, including one in ten (10%) with operating margins of at least 15%. Operating margins were higher among rural for-profit than rural non-profit hospitals (8.5% versus 3.5%) and lower (0.3%) among rural government hospitals. Operating margins were also higher among system-affiliated versus independent rural hospitals (4.8% versus 0.6%, respectively).

Operating margins were lower among hospitals with Medicare rural designations than other hospitals. Low-volume hospitals (hospitals with few discharges that are a minimum distance from other facilities) and Medicare dependent hospitals (small rural hospitals with high Medicare inpatient shares) had the lowest operating margins (1.7% and 1.8%, respectively) (Figure 7). Operating margins were also lower on average among critical access hospitals (rural hospitals with at most 25 beds that with some exceptions are a minimum distance from other facilities) and sole community hospitals (hospitals that are the only source of short-term, acute inpatient care in a region) relative to hospitals without a Medicare rural designation (4.1% and 4.2%, respectively, versus 5.7%). About half of low-volume, Medicare dependent and sole community hospitals had negative operating margins in 2023 (52%, 52%, and 49%, respectively), as did 40% of critical access hospitals. A smaller share (35%) of hospitals without a Medicare rural designation had negative operating margins.
Operating Margins Were Lower Than Average Among Rural Hospitals in 2023

Senators Cassidy and Hassan recently released a framework for site-neutral payment reforms that some of the savings be reinvested into sole community, low-volume, and Medicare dependent hospitals. As noted above, each of these groups had lower operating margins than did hospitals without a rural designation. The framework does not mention new funds for critical access hospitals, which would likely be exempt from site-neutral payment reforms.

Policymakers have had ongoing concerns about the financial health of rural hospitals and the implications for access to care and the local economy. At the same time, it may be difficult to sustain some rural hospitals—such as those in areas with shrinking populations—and some have argued that care in at least some scenarios should be moved towards other settings, including telehealth, outpatient facilities, and larger regional hospitals.

Operating Margins Were Higher Than Average Among Hospitals With a Large Number of Beds and Among Minor Teaching Hospitals in 2023

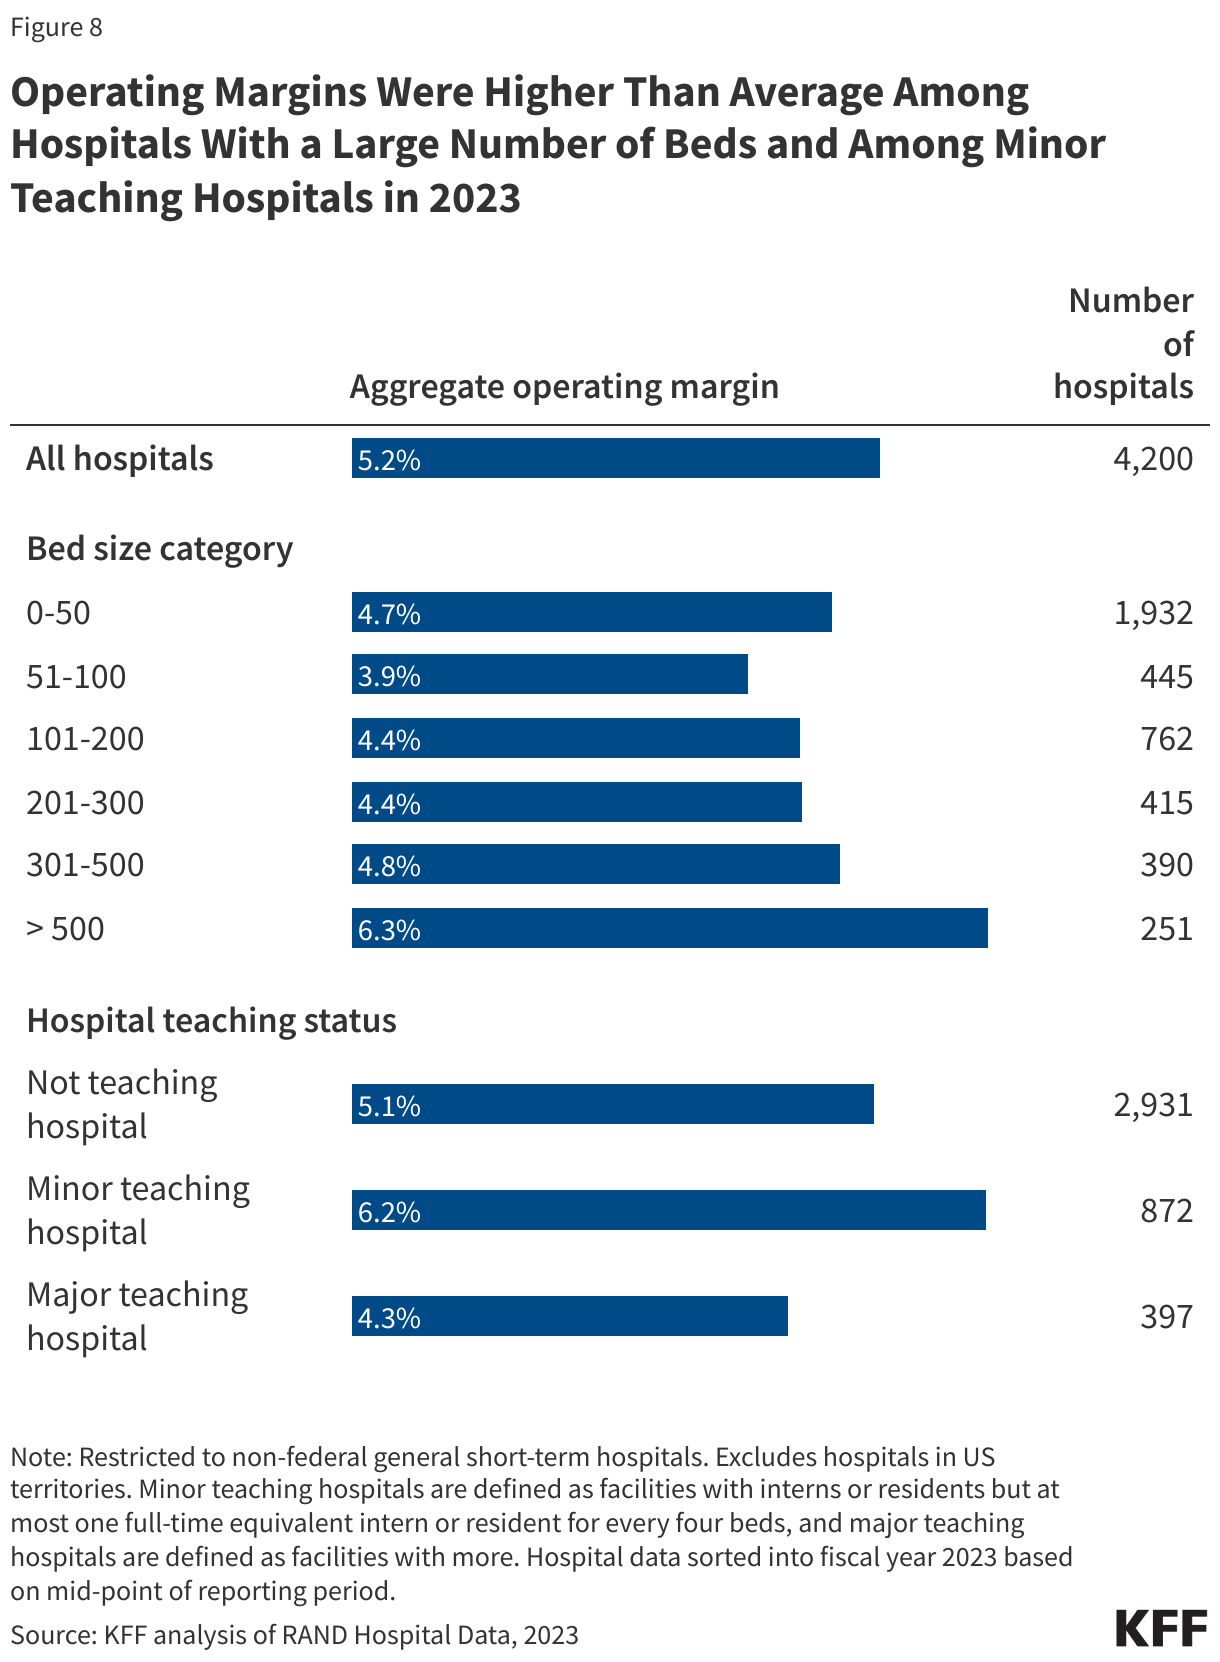
Hospitals with greater than 500 beds had higher operating margins (6.3%) than those with fewer beds (e.g., 3.9% among hospitals with 51 to 100 beds) (see Figure 8). Minor teaching hospitals had higher margins (6.2%) than major teaching (4.3%) and non-teaching (5.1%) hospitals. Minor teaching hospitals are defined as facilities with interns or residents but at most one full-time equivalent intern or resident for every four beds, and major teaching hospitals are defined as facilities with more.
Operating Margins Were Higher Than Average Among Hospitals With a Large Number of Beds and Among Minor Teaching Hospitals in 2023

Operating Margins Varied Across States in 2023

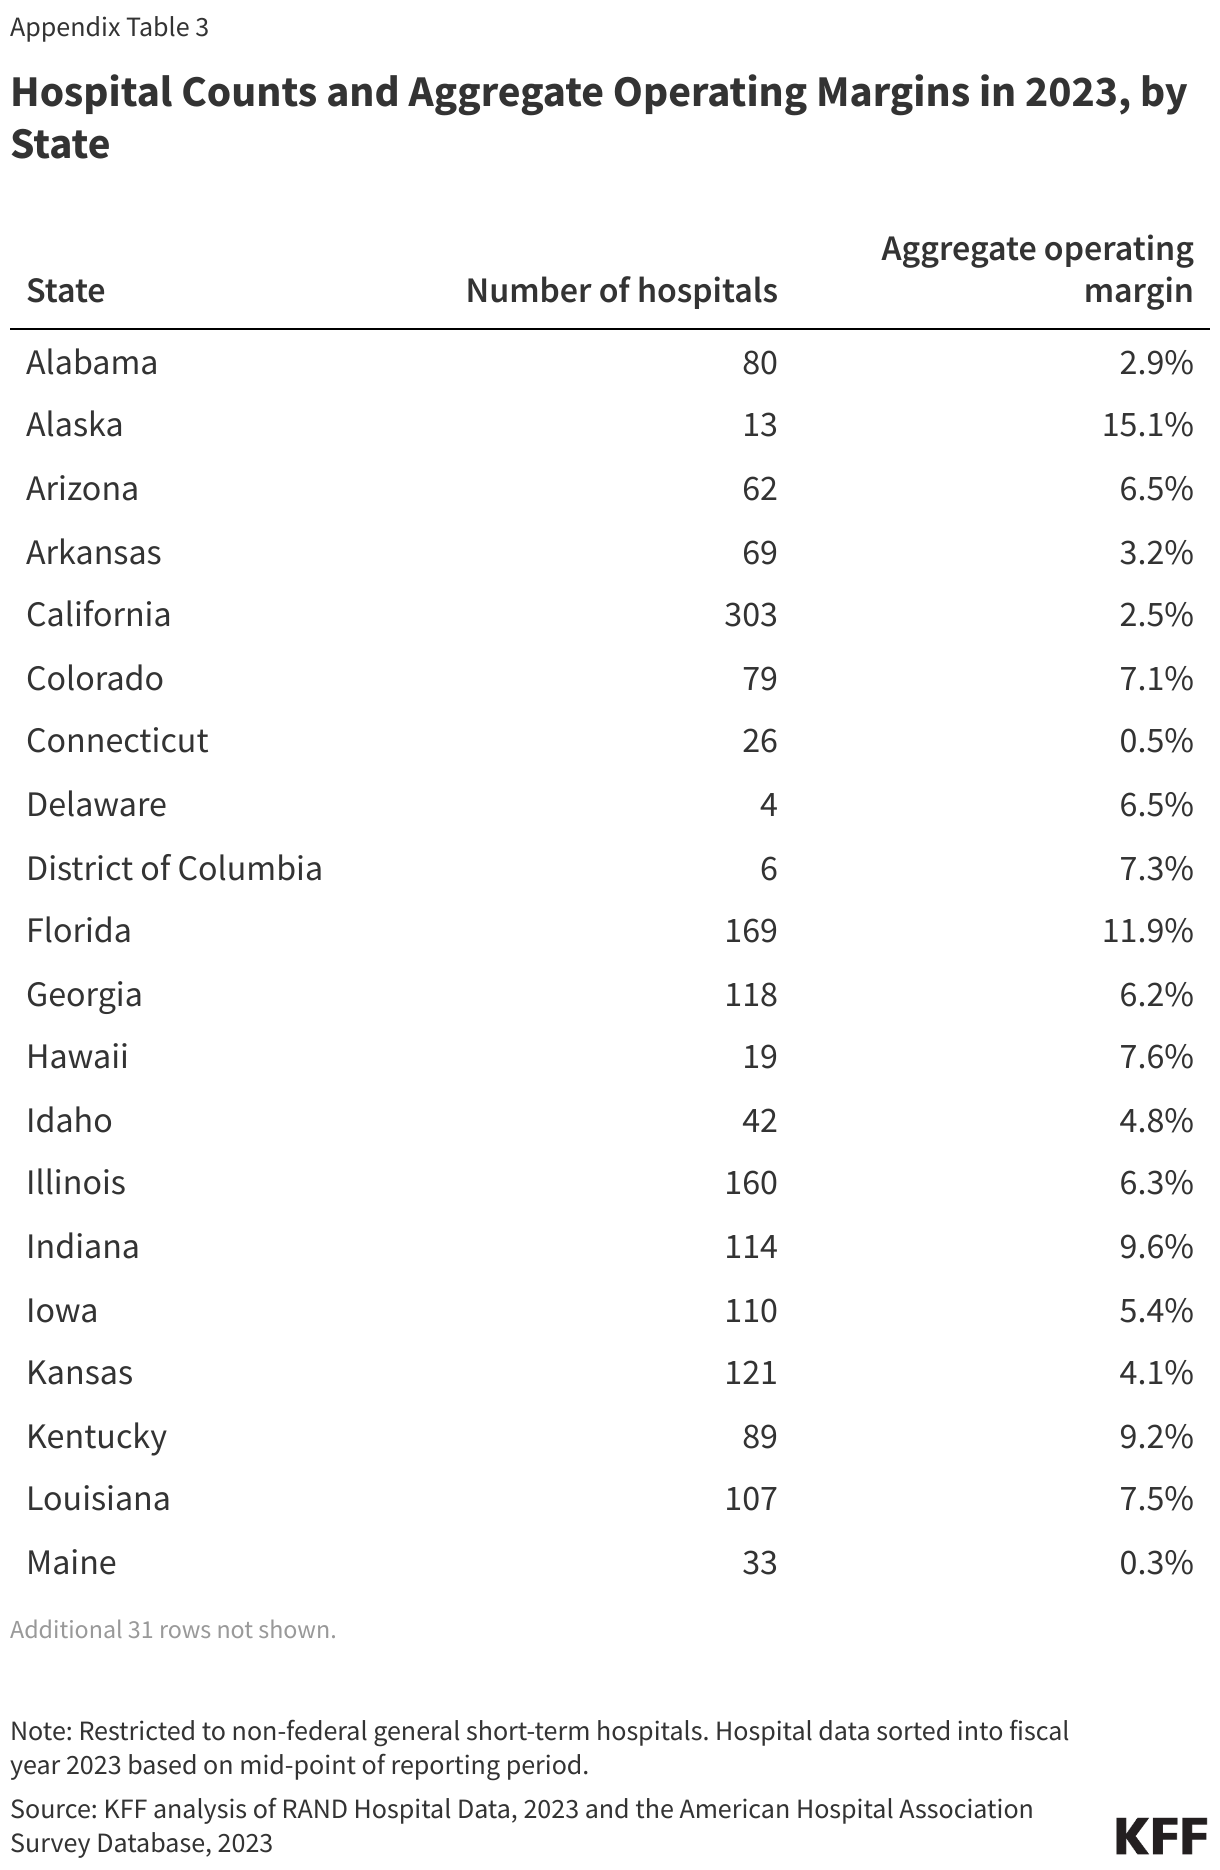
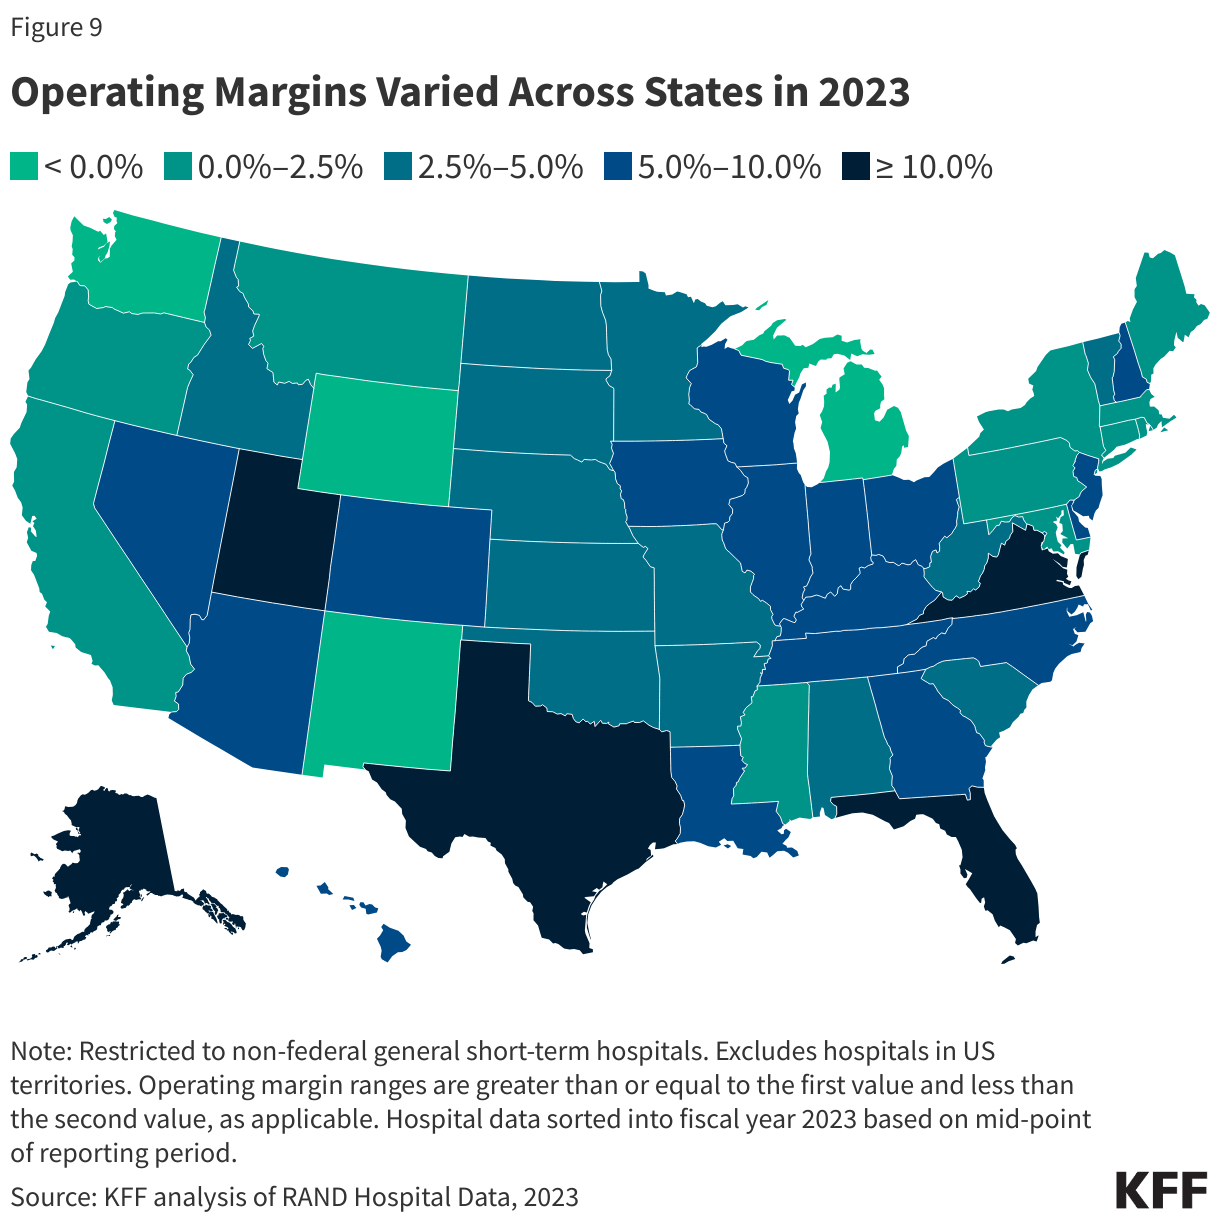
Aggregate operating margins were at least 10% in five states (Alaska, Florida, Texas, Utah, and Virginia) but negative in four states (Michigan, New Mexico, Washington, and Wyoming) (see Figure 9). Differences likely reflect a variety of unique state circumstances, such as demographics, hospital ownership and cost structure, commercial reimbursement rates, and state and local health and tax policy. For instance, operating margins may have been high in Texas in part because the state has a relatively large number of for-profit hospitals (which have higher operating margins on average), among other factors. The same is true of Florida, which may have also had high operating margins in part due to the relatively high commercial prices in the state. As an example of a state on the other end of the spectrum, margins may have been relatively low in Wyoming in part because the vast majority of hospitals are in rural areas (92% compared to 40% of all hospitals), among other factors. It is also possible that a small number of hospitals with large revenue could have a large impact on aggregate operating margins, especially in states with relatively few hospitals, like Alaska.
Operating Margins Varied Across States in 2023

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

Methods

Hospital financial information was obtained from RAND Hospital Data, a cleaned and processed version of annual cost reports that Medicare-certified hospitals are required to submit to the federal government. Cost reports were assigned to fiscal years based on the mid-point of the reporting period. Most 2023 cost reports in this analysis had reporting periods that ran from January to December 2023 (41%), July 2022 to June 2023 (32%), or October 2022 to September 2023 (17%).

The analysis included a number of sample restrictions. All analyses focused on non-federal general short-term hospitals not in US territories. This left 4,471 hospitals in 2023. Dropping cost reports that were less than or longer than a year left 4,337 hospitals in 2023. Dropping hospitals in years with missing, questionable, or certain outlier values left 4,200 cost reports for 2023, which represents 94% of non-federal general short-term hospitals not in US territories in the data. Some analyses of hospital characteristics included fewer hospitals based on the data available (see counts in Appendix Table 2). For example, price data, which are discussed below, were only available for 2,779 hospitals.

Total margins for hospitals overall or a specific group of hospitals were defined as net income (revenues minus expenses) divided by revenues. Operating margins were approximated by calculating the same ratio as for total margins after removing reported investment income and charitable contributions from revenues, in line with the approach used by MedPAC. This approximation may include other nonoperating revenues (such as from the sales of assets) as well as nonoperating expenses for a given hospital. It is possible that this approach could understate or overstate operating margins and that it may do so to a different degree over time and across hospitals, which would affect observed trends and hospital comparisons.

Aggregate margins for hospitals overall or a specific group of hospitals were calculated based on total relevant revenues and expenses for the given set of hospitals. Aggregate margins are equivalent to the average margin after weighting hospitals by their revenue (i.e., they give more weight to hospitals with greater revenue). Aggregate operating margins were larger than unweighted average operating margins in 2023 (5.2% versus 2.9%) and exhibited a larger increase from 2022 and 2023 (from 2.7% in 2022 to 5.2% in 2023 versus from 2.3% in 2022 to 2.9% in 2023 when evaluating unweighted averages). This implies that operating margins and increases in margins were higher on average among hospitals with more revenue. The relationship between margins and hospital characteristics was generally in the same direction when looking at either aggregate or unweighted average margins, though the magnitude differed.

We relied on additional datasets for certain hospital characteristics. We obtained geographic classifications from Census Bureau data. Rural and urban were defined as nonmetropolitan and metropolitan areas, respectively. Metropolitan areas represent a county or group of counties that contains at least one urban area with a population of 50,000 or more. The analysis also describes margins in micropolitan areas, which represent a county or group of counties that contains at least one urban area with a population of at least 10,000 but less than 50,000. We obtained hospital facility price data (combined inpatient and outpatient) from Round 5.1 of the RAND Price Transparency Study, which uses 2020-2022 claims data from a large population of commercial patients. These data were available for 2,779 hospitals in this analysis. We also relied on the AHA Annual Survey Database to obtain 2023 data on payer mix, system membership, and hospital referral region (HRR) market shares. For HRR market shares, we focused on available admissions data for non-federal general, short-term hospitals that could be matched to an HRR.

As noted, the share of patients covered by Medicaid may signal the extent to which a given hospital cares for a disproportionate share of low-income patients. This is complicated by the fact that Medicare-Medicaid enrollees are likely categorized as Medicare (rather than Medicaid) admissions and that Medicaid eligibility requirements vary across states. However, differences in aggregate operating margins based on Medicaid shares were similar when looking at Medicaid as a share of patients who are not enrolled in Medicare and adjusting for differences across states (3.0% versus 7.4% among the top versus bottom quarter of Medicaid shares).

There are a number of data sources on hospital and health system finances, and each has limitations. For example, audited financial statements are considered the gold standard of financial data, but they often do not break out information about individual hospitals in the common scenario where facilities are part of a broader health system. They also are not easily accessible, and they typically require laborious, specialized expertise to standardize financial information across systems.

There are also tradeoffs when using cost report data. Cost reports are unique in that they provide facility-level information for the vast majority of community hospitals, which is why we relied on them for this analysis. However, they include less detailed and standardized data than audited financial statements for calculating margins. For example, cost reports do not fully separate out finances related to operating versus nonoperating activities, which requires that operating margins be approximated. Further, cost reports do not undergo the same rigorous auditing process as audited financial statements and do not include system-level data that may have a bearing on the finances of member hospitals.

Appendix

Interactive Datawrapper Embed
Hospital counts and average operating margins in 2023, by characteristics
Hospital counts and average operating margins in 2023, by state

The Impact of HIV on Women in the United States

Published: Dec 16, 2024

Key Facts

  • Women have been affected by HIV since the beginning of the epidemic and face unique challenges in accessing optimal prevention, care, and treatment resources.1 
  • In 2022, women accounted for about 1 in 5 (19%) new HIV diagnoses in the U.S.2 
  • Women of color, particularly Black women, have been disproportionately impacted and represent the majority of women living with HIV, as well as the majority of new diagnoses among women.
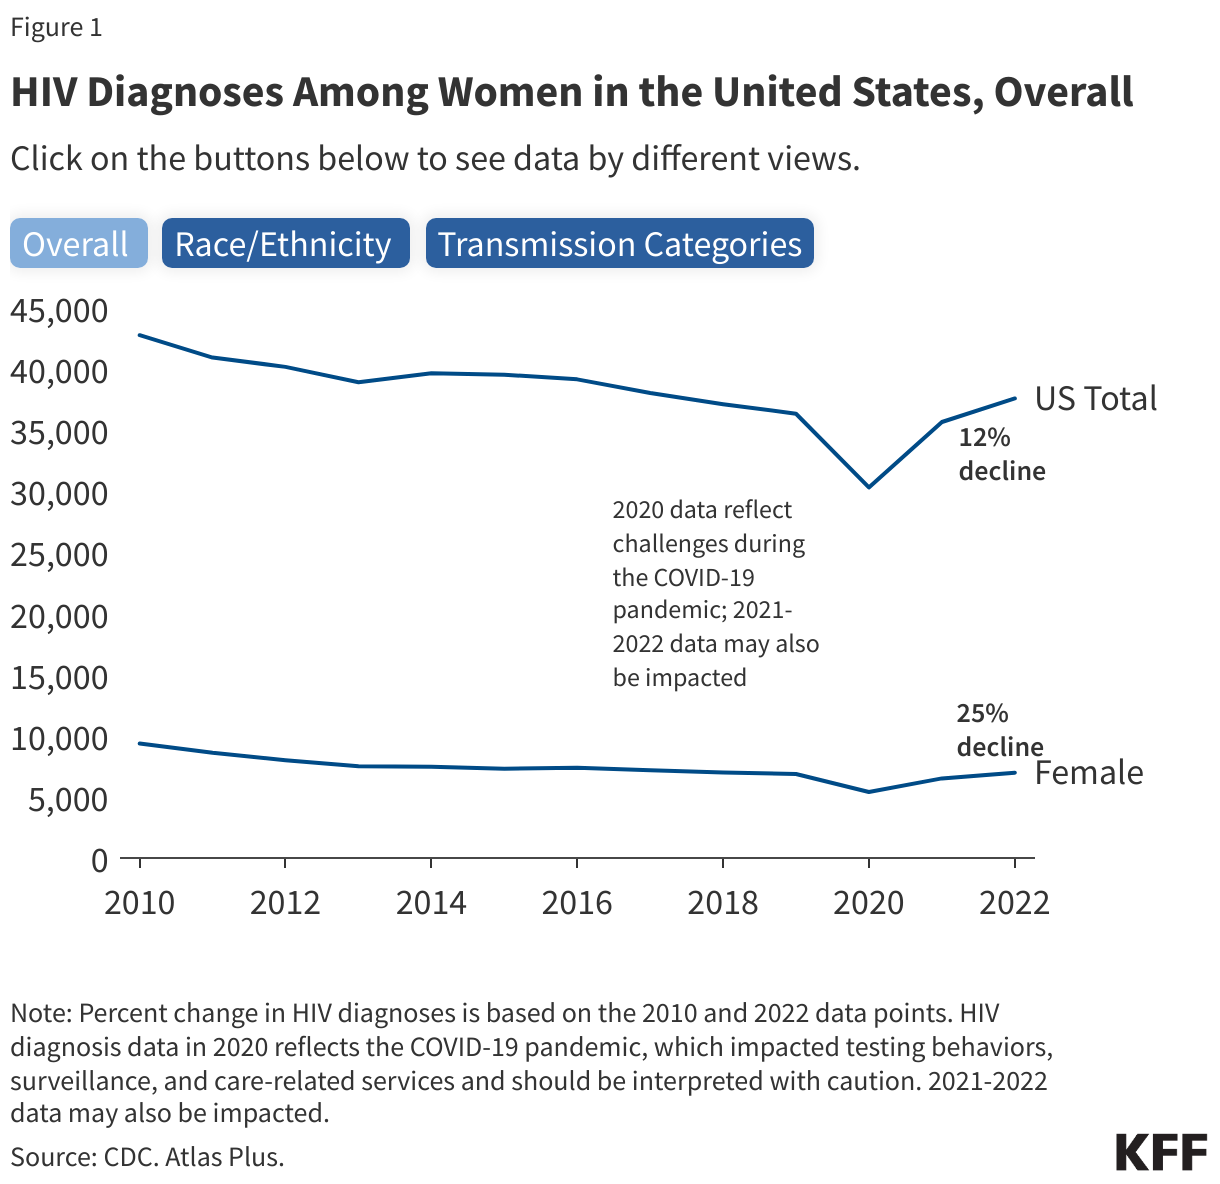
  • Recent data indicates that HIV diagnoses among women fell 25% between 2010 and 2022, compared to a 12% decline across the population overall. Decreases in HIV diagnoses have occurred for nearly every racial/ethnic group besides White women (Figure 1). However, rates of HIV diagnoses among women of color are much higher.
HIV Diagnoses Among Women in the United States, Overall

Overview

  • Today, there are more than 1.2 million people estimated to be living with HIV in the U.S., including 268,800 (22%) who are women.
  • Women accounted for 19% of the 6,980 new HIV diagnoses in 2022 and are diagnosed with HIV at slightly older ages than men are.
  • Between 2010-2022, while HIV diagnoses decreased by 12% among the population overall, the decline was twice as large among women (25%). Decreases in HIV diagnoses have occurred for nearly every racial/ethnic group besides White women (Figure 1). However, rates of HIV diagnoses among women of color are much higher.
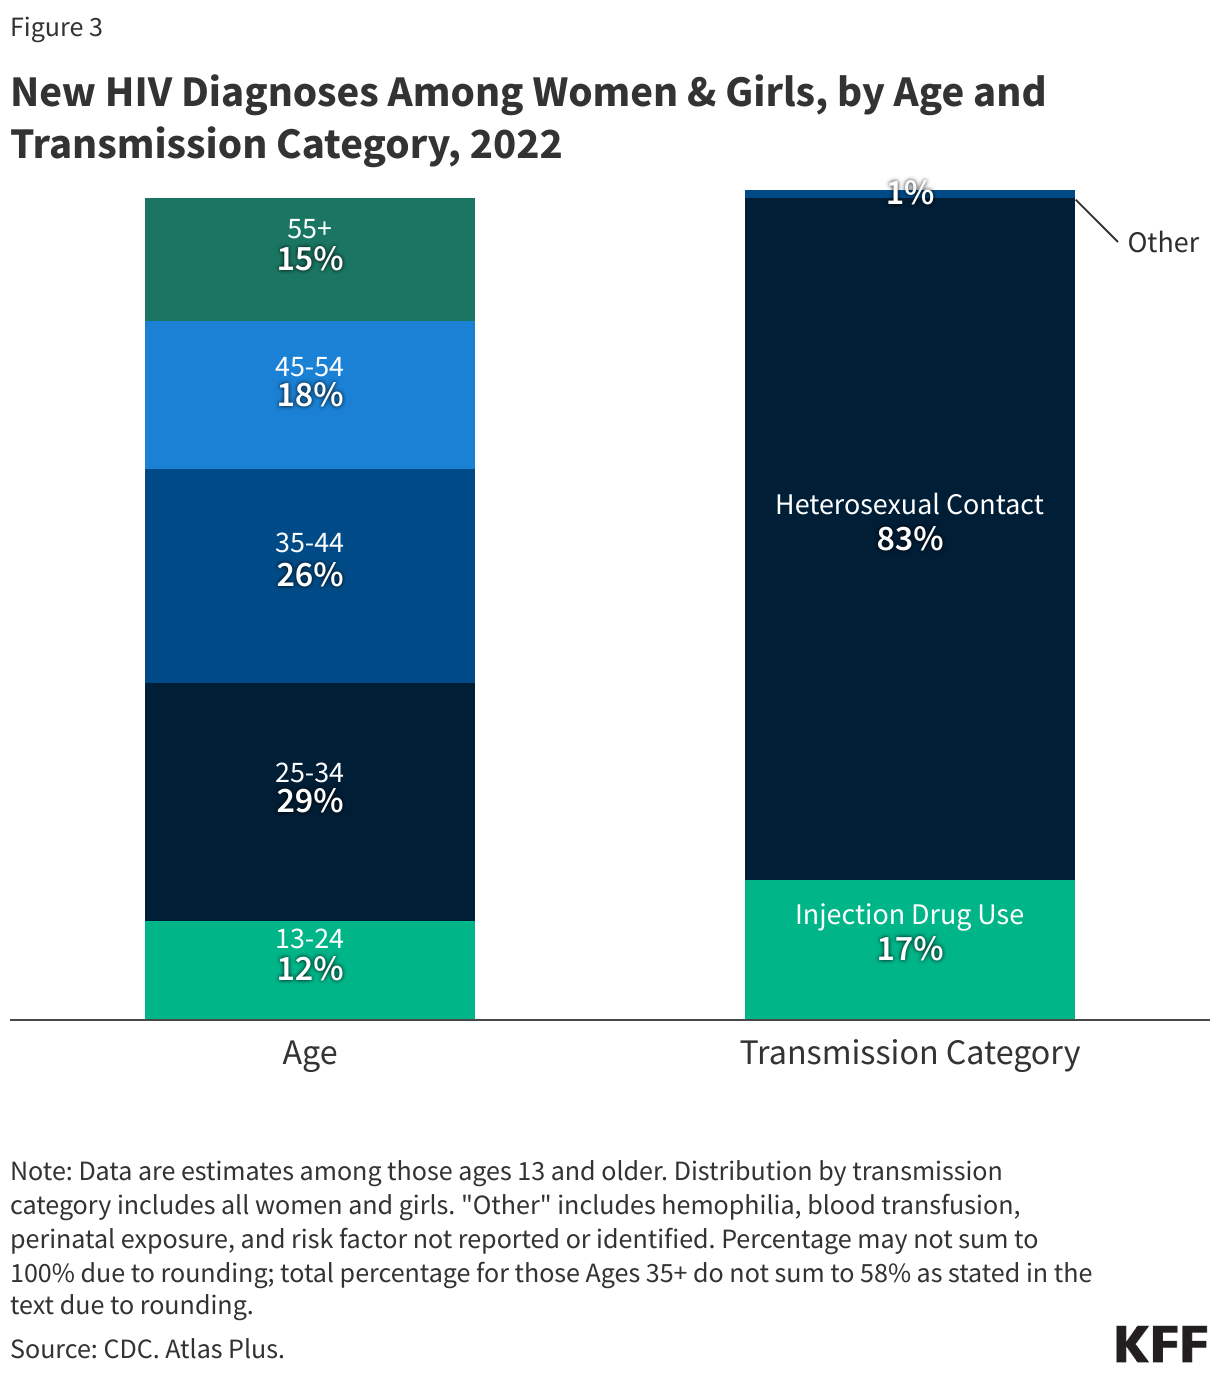
  • Of new HIV diagnoses among women in 2022, 83% were attributable to heterosexual sex, 17% were attributable to injection drug use, and 1% were attributed to other causes.
  • Women with and at risk for HIV face several challenges to getting the services and information they need, including socio-economic and structural barriers such as poverty, cultural inequities, and intimate partner violence (IPV).

Race/Ethnicity

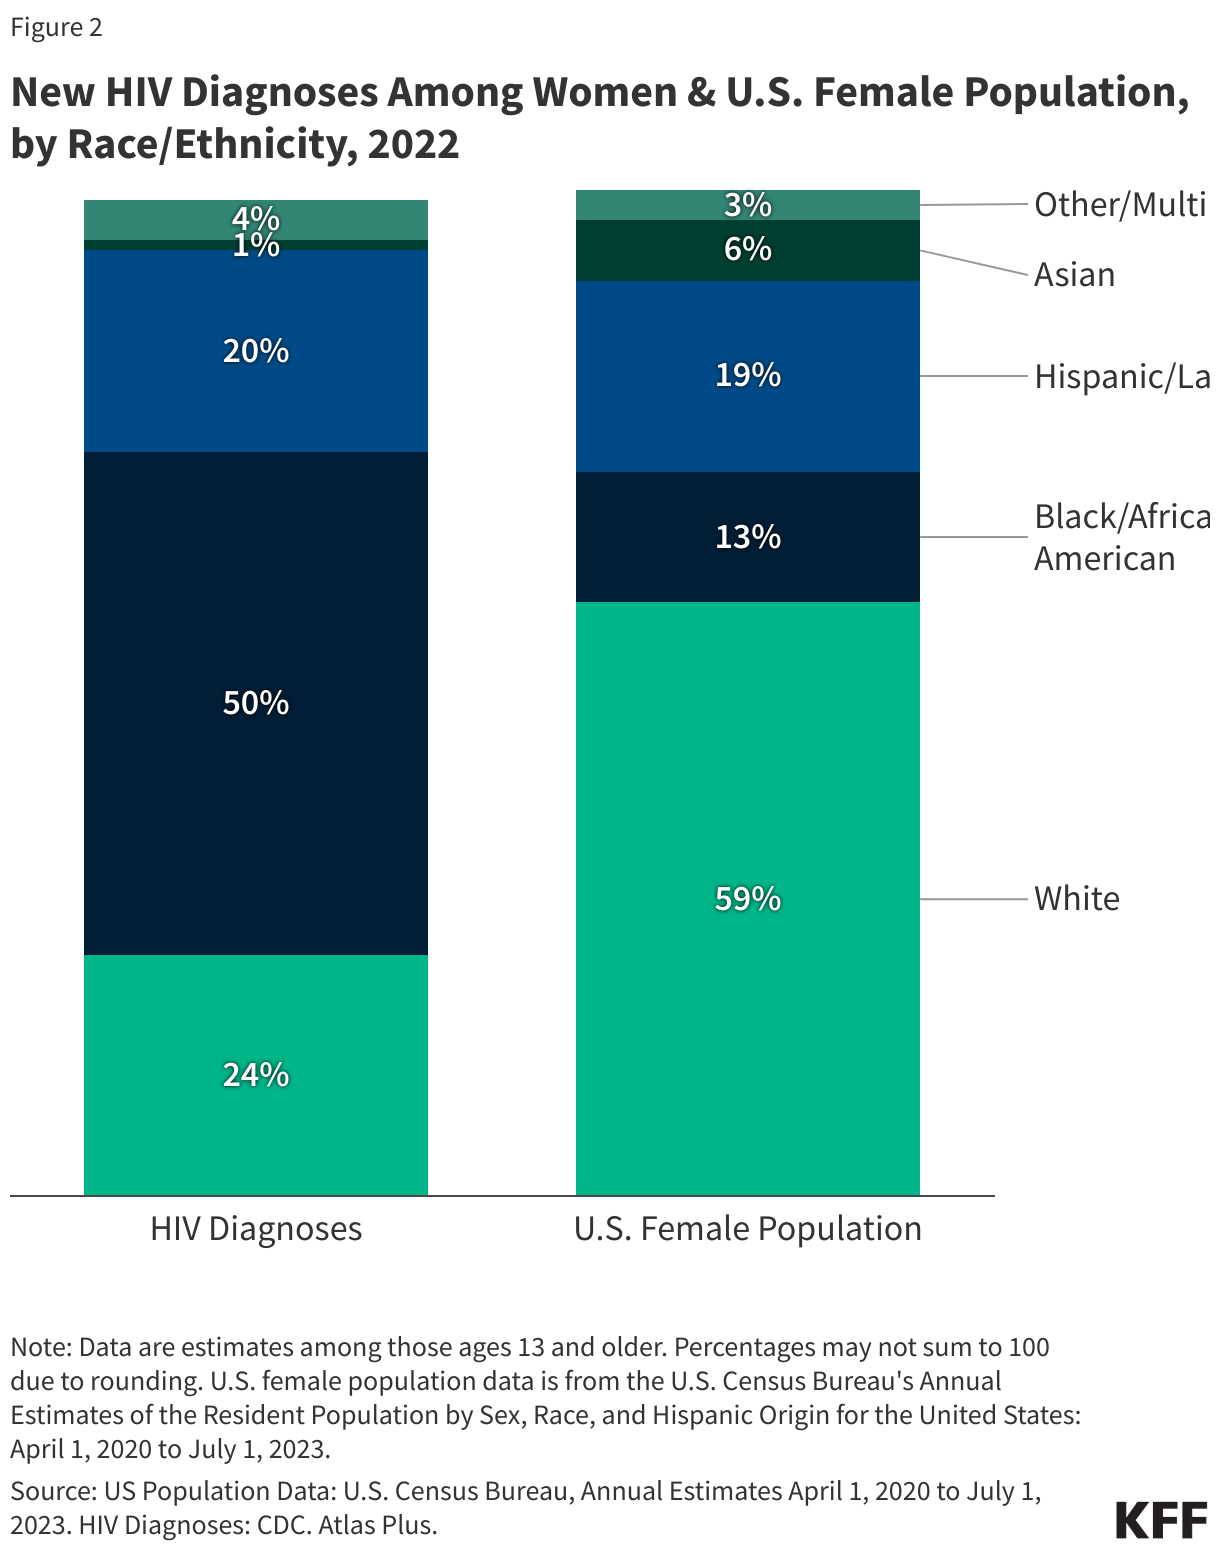
  • Women of color, particularly Black women, are disproportionately affected by HIV, accounting for the majority of new HIV diagnoses, the majority of women living with HIV, and highest rates of HIV-related deaths among women with HIV in the U.S.
  • In 2022, Black women accounted for half (50%) of HIV diagnoses among women, while only accounting for 13% of the U.S. female population. White women accounted for 24% and Hispanic/Latina women accounted for 20% of HIV diagnoses among women (Figure 2).
  • HIV diagnoses decreased 58% among Multiracial women, 39% among Black women, 9% among Hispanic/Latina women, and 3% among Asian women between 2010 and 2022. In this same timeframe, HIV diagnoses increased 21% among White women.
  • Rates of new HIV diagnoses are much higher for Black, Multiracial, and Hispanic/Latina women than for White women. In 2022, the rate of new HIV diagnoses for Black women was 10 times higher than the rate for White women (19.2 per 100,000 compared to 1.9); the rate for Multiracial women (8.2) was 4 times higher; the rates for Hispanic/Latina women (5.5) and American Indian/Alaska Native women (5.5) were nearly 3 times higher; the rate for Native Hawaiian/Other Pacific Islander women (4.6) was more than 2 times higher. The rate of new HIV diagnoses among Asian women (1.1) was less than that of White women (1.9).
  • In 2021, HIV was the 9th leading cause of death for Black women ages 25-34, behind diabetes. Black women accounted for the greatest share of deaths (of any cause) among women with diagnosed HIV in 2022 (57%), followed by White women (20%), and Hispanic/Latina women (15%).
New HIV Diagnoses Among Women & U.S. Female Population, by Race/Ethnicity, 2022

Age

  • Women ages 25-34 accounted for the largest share (29%) of HIV diagnoses among women in 2022, followed by those ages 35-44 (26%). (Figure 2).
  • Women are diagnosed with HIV at slightly older ages than men are. Women 35 years old and older accounted for 58% of new diagnoses among women in 2022. Comparatively, men in this age group accounted for 41% of diagnoses among men.
New HIV Diagnoses Among Women & Girls, by Age and Transmission Category, 2022

Transmission

  • In 2022, HIV diagnoses among women were mostly attributed to heterosexual sex (83%), followed by injection drug use (17%), and 1% were attributed to other causes. Heterosexual transmission accounts for a greater share of HIV diagnoses among Black and Hispanic/Latina women (90% and 87%, respectively) compared to White women (64%). Among White women, injection drug use accounts for a greater share of diagnoses (36%), relative to Black and Hispanic/Latina women (9%, 12%). (See Figure 3.)
  • Mother-to-child transmission of HIV in the U.S. has decreased dramatically since its peak in 1991 due to antiretroviral therapy (ART), which significantly reduces the risk of transmission from a woman to her baby (to 1% or less). Still, some perinatal infections occur each year, the majority of which are among Black women, and there continues to be missed opportunities for preventing mother-to-child transmissions, such as testing late in pregnancy. Of the 42 infants born with HIV in 2022, two-thirds (67%) were Black.

Geography

  • Although HIV diagnoses among women have been reported throughout the country, the impact of the epidemic is not uniformly distributed.
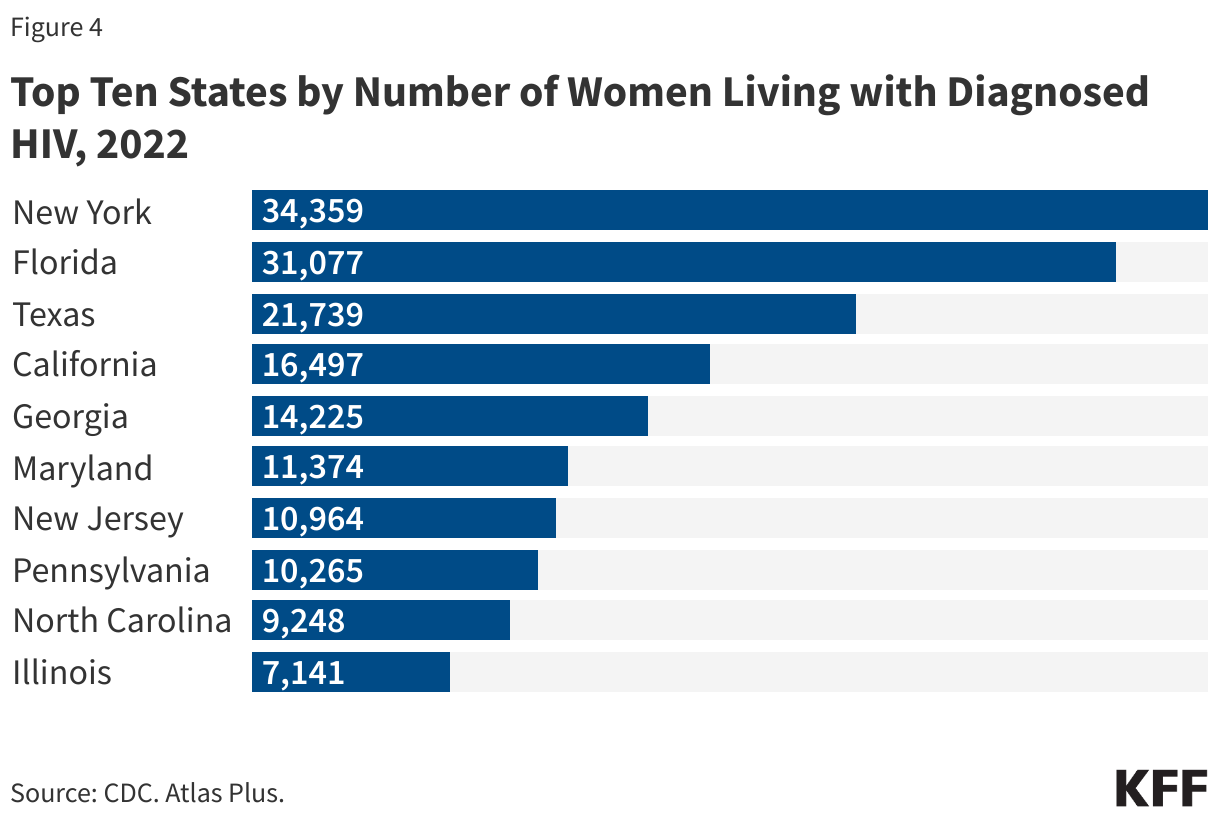
  • Ten states account for two-thirds of women living with diagnosed HIV (67% in 2022); with 5 states accounting for nearly half (47%) (Figure 4). While the District of Columbia ranked 18th among states in terms of the number of women living with diagnosed HIV (3,629 in 2022), the rate per 100,000 women living with an HIV diagnosis was the highest, nearly 7 times the national rate for women (1,189 per 100,000 compared to 174 per 100,000 nationally), similar to the share in other high populous urban areas.
  • Thirty-five counties account for almost half (46%) of all women living with an HIV diagnosis in the U.S., with Bronx County, New York having the greatest number (9,454) and highest rate (1,552 per 100,000) of women living with an HIV diagnosis.
Top Ten States by Number of Women Living with Diagnosed HIV, 2022

Transgender Women

  • Transgender women are disproportionately affected by HIV and face stigma, discrimination, and exclusion in accessing testing, treatment, and health care, relative to other women.
  • Since the beginning of the HIV epidemic, national surveillance of and research on the impacts of HIV on transgender women, as well as transgender and gender-diverse people more broadly, has been limited.
  • Although transgender women account for a small share of people estimated to be living with HIV (1%) among transgender women, 14% are estimated to be living with HIV.
  • In 2022, transgender women accounted for 87% of 994 new HIV diagnoses among transgender and gender-diverse people. Among transgender women, looking across race/ethnicity, Black transgender women had the highest share of HIV diagnoses (41%), followed by Hispanic/Latina transgender women (39%), whereas White transgender women accounted for 13% of diagnoses. HIV diagnoses among transgender women were mostly attributed to sexual contact (89%).
  • Among transgender women, 83% received care for HIV, while 67% were virally suppressed, similar to the share in the overall population of people with HIV.

Sexual and Reproductive Health

  • HIV interacts with women’s reproductive health on many levels, impacting menstruation, reducing fertility, and predisposing pregnant people to greater risk of complications. In addition, antiretroviral therapy may impact contraceptive efficacy. During pregnancy, people with HIV can take additional measures to prevent mother-to-child-transmission of HIV such as adherence to antiretroviral regimens and labor and delivery procedures.
  • Mothers living with HIV can reduce the risk of transmission to their babies via breastfeeding to less than 1% through antiretroviral therapy.
  • Women with other sexually transmitted infections (STIs) are at increased risk for contracting HIV. Women with HIV are at increased risk for developing or contracting a range of conditions, including human papillomavirus (HPV), which can lead to cervical cancer, and severe pelvic inflammatory disease.
  • Sexual and reproductive health clinics provide an important entry point for reaching women at risk for and living with HIV. Nearly two-thirds (63%) of women receiving care at sexual and reproductive health clinics report it as their usual source of medical care.
  • Research efforts are exploring a number of new HIV prevention technologies which could be particularly beneficial for women, such as cervical barriers and microbicides. The long-acting injectable lenacapavir has also been shown to be highly effective in preventing HIV among women but is not yet approved in the U.S. Once approved, this will be an important addition to the prevention toolkit for women, particularly given its relatively low burden of twice annual injections.

Intimate Partner Violence (IPV) and HIV

  • Women living with HIV are disproportionately affected by intimate partner violence (IPV), including physical, sexual, and emotional abuse compared to the general population. Intimate partner violence (IPV), sometimes referred to as domestic violence, has been shown to be associated with increased risk for HIV among women, as well as poorer treatment outcomes for those who are already positive.
  • In the U.S., 35% of women living with HIV experienced physical (i.e. non-sexual) IPV in their lifetime, compared to 24% of men living with HIV.
  • In many cases, the factors that put women at risk for HIV are similar to those that make them vulnerable to experiencing trauma or IPV: women in violent relationships are at a greater risk for contracting STIs, including HIV, than women in non-violent relationships, and women who experience IPV are more likely to report risk factors for HIV. These experiences are interrelated and can become a cycle of violence, HIV risk, and HIV acquisition.
  • Women may also be at increased risk of experiencing violence upon disclosure of their HIV status to partners.

HIV Prevention

  • The CDC recommends routine HIV screening for all adults, including women, ages 13-64, in health care settings, as well as repeat screening at least annually for those at high risk. The CDC also separately recommends that all pregnant women be screened for HIV, and that those at high-risk for HIV have repeat HIV screening in the third trimester. Testing of newborns is also recommended if the mother’s HIV status is unknown.
  • Additionally, the United States Preventive Services Task Force (USPSTF) recommends HIV testing (including specifically for pregnant women), IPV screening, many STI screenings, and pre-exposure prophylaxis (PrEP) which means that most insurers are required to cover these services without cost-sharing.
  • Despite these recommendations, only 37% of women in the U.S. ages 18-64 report having been tested for HIV at some point. Black women are much more likely to report having been tested in the past year compared to White women (21% compared to 6%).
  • PrEP is a safe and highly effectivepreventive medication that reduces the risk of acquiring HIV through sex by 99%. Women have been underrepresented in PrEP uptake and use and not all forms of PrEP are approved for people assigned female at birth. Recent developments in PrEP research have shown lenacapavir to be highly effective in preventing HIV among cisgender and transgender women.

Access to Care & Treatment

  • As is the case for all people, there are several sources of care and treatment for women living with and at risk for HIV in the U.S., including government programs such as Medicaid, Medicare, and the Ryan White Program for those who are eligible.
  • Looking across the care continuum, women see progress but continue to face challenges related to diagnosis, linkage to care, and viral suppression. At the end of 2022, among all women living with HIV, 90% were diagnosed, 48% were retained in care, and 57% were virally suppressed, similar to the shares among men.
  • Among women with HIV, 21% were diagnosed late – that is, were diagnosed with AIDS within 3 months of testing positive for HIV, the same share as among men. This suggests that one in five women are not adequately being served by HIV testing services and are not getting into care within ideal timeframes.
  1. Unless otherwise noted, the term “women” in this factsheet refers to sex assigned at birth. ↩︎
  2. Unless otherwise noted, HIV data come from KFF analysis of the Centers for Disease Control and Prevention (CDC) data in the CDC’s National Center for HIV, Viral Hepatitis, STD, and Tuberculosis Prevention tool: Atlas Plus. https://www.cdc.gov/nchhstp/about/atlasplus.html ↩︎

Potential Health Policy Administrative Actions in the Second Trump Administration

President-elect Trump could exercise executive branch authority through administrative action to quickly move forward on some policy changes without congressional action.

Published: Dec 16, 2024

This is a quick guide to potential health policy administrative actions under the incoming Trump administration based on campaign positions and statements by President-elect Trump, President Trump’s record during his first administration, and expected actions that would reverse or modify regulations or guidance issued by the Biden administration. Click the + to expand for details of each potential action.

Note: This is not an exhaustive list of possible administrative actions by President-elect Trump and the guide may be updated as new information becomes available up until his inauguration on January 20, 2025.

Affordable Care Act


Abortion


Contraception


Medicaid


Immigration and Health


LGBTQ Health Policy

Public Health

Racial Health Equity and DEI Initiatives


Global Health


Prescription Drugs


Fentanyl


Long-term Care


Water Fluoridation in the U.S.: The Federal Role in Policy and Practice

Authors: Josh Michaud, Jennifer Kates, and Nambi Ndugga
Published: Dec 13, 2024

Introduction

Fluoridating water has been a long-standing public health practice in most communities across the U.S. and has been supported and recommended by the federal government for decades. Even so, ever since the first U.S. community began fluoridating its water in 1945 there have also been concerns raised about this practice and many communities choose not to fluoridate. In recent years, in fact, there has been growing scrutiny of the practice, and debates in many parts of the country about whether to continue fluoridation. President-elect Trump’s announced nomination of Robert F. Kennedy Jr. to be the Secretary of Health and Human Services has raised questions about the potential for the federal government to influence water fluoridation practices across the country. Kennedy has long been critical of water fluoridation and has said the incoming Trump administration will recommend that fluoride be removed from public water on day one. Meanwhile, key professional associations, public health experts, and many policymakers continue to support fluoridation as an important tool for improving dental health in the U.S., and perhaps one of the most important public health interventions ever implemented.

To help inform policy discussions about this topic, this brief provides an overview of the role of the federal government in water fluoridation decisions and the current status of water fluoridation in the U.S. While the federal government cannot require communities to fluoridate their water or remove fluoridation already in place, it does regulate maximum levels and provides guidance to state and local communities on optimal levels of fluoride. If guidance were to change – for example, suggesting that fluoride was not recommended — it could have ripple effects across the country.

The Federal Government’s Role and Current Recommendations for Water Fluoridation

The federal government does not have legal authority to require state and local communities to fluoridate their water, nor to remove fluoridation in areas where it is already policy. Instead, these decisions – just like many public health policy decisions in the U.S. – are made at the state and local levels. There are some states (for example: California, Delaware, Georgia, Illinois, Kentucky, Louisiana, Minnesota, Mississippi, Nebraska, Nevada, Ohio and South Dakota) that require water systems of a certain size within their state to provide fluoridated water, while others leave this decision to city, county, or other officials or leave the choice up to voters who decide via local referendums. At the same time, the federal government – specifically the Environmental Protection Agency (EPA) – does have the primary authority to set and regulate the maximum level of fluoridation in public water systems.

The federal government reviews data and other evidence about the safety and effectiveness of fluoridation and issues recommendations and guidance on best practices for state and local decision-makers to consider. The Department of Health and Human Services (HHS), in particular the Centers for Disease Control and Prevention (CDC), provides recommendations about best practices for achieving public health benefits from fluoridation. The first federal guidelines regarding fluoridation of water systems came from the U.S. Public Health Service (USPHS) in 1945, with a recommended maximum concentration level. Updated guidelines in 1962 revised this maximum, and included, for the first time, a recommended fluoride level, citing its ability to prevent dental caries; the most recent update to these federal guidelines was in 2015.

The federal government also sets and enforces nationwide standards for maximum allowable fluoridation levels. The EPA, acting via the authority provided through the Safe Drinking Water Act of 1974, is responsible for setting federal standards for maximum fluoridation levels in water systems to protect against risks from excessive exposure to fluoride. This includes setting a primary, legally enforceable standard for water fluoridation levels, and a secondary “non-enforceable” standard. If a water system’s fluoridation levels exceed the primary enforceable standard, legal action can be taken against the water provider; if levels exceed the secondary, non-enforceable standard, it does not trigger legal or federal action, but public notice of the exceedance must be provided to persons served by the system no later than 12 months after the levels were exceeded. EPA delegates this regulatory and enforcement authority to states that meet certain capacity requirements. States may also set their own maximum fluoride levels, as long as they are at least as stringent as federal standards.

Current HHS/USPHS guidelines (last updated in 2015) recommend an optimal fluoride concentration of 0.7 mg per liter (mg/L) in community water systems (CWS) while EPA regulations set the primary standard for the maximum level of fluoride in water systems at 4.0 mg/L and the secondary, non-enforceable standard at 2.0 mg/L. Both HHS/CDC and the EPA have discretion to update their guidance and recommendations and have done so in the past. Updating the USPHS guidelines involves a years-long, interagency and multi-stakeholder process that is likely to include review and input from external experts and a period for public comment and discussion. For example, following an internal process that developed its initial updated fluoridation recommendations, HHS published its proposed changes in 2011.  After further review and public comment periods, the final updated recommendations were published in 2015, and included a change to the recommended fluoride concentration in CWS, from 1.2 mg/L to 0.7 mg/L. The EPA set its 4.0 mg/L primary standard for fluoride in 1986, and by law the agency is required to review of drinking water standards (including fluoridation standards) at least every six years. The EPA’s most recent review of drinking water standards, released in July 2024, concluded that the current maximum fluoride level guideline is “not a candidate for revision at this time.” In the future, the EPA could decide to initiate a new review and assessment process for its fluoride guidelines.

Benefits and Risks from Water Fluoridation

Water fluoridation has been found to be effective in reducing the risk and severity of dental caries (tooth decay) in children (as well as adults). According to CDC, a review of the best available evidence shows water fluoridation reduces tooth decay by about 25% in children and adults, and evidence also shows that children living in communities where water is fluoridated have, on average, more than two fewer decayed teeth compared to similar children living in non-fluoridated communities. A comprehensive review of relevant studies, updated in 2024, concluded that evidence shows that initiation of water fluoridation reduces dental caries in children. A study from Juneau, Alaska found that cessation of fluoridation in that community was associated with increases in the number of dental caries, and the number of related procedures and treatments among Medicaid-eligible children.

At the same time, questions have been raised about health risks from exposure to high levels of fluoride concentrations, beyond current federal standards. Extended exposure to high levels of fluoride may have negative effects, such as contributing to dental fluorosis, a discoloration of teeth in young children. Recently, there have been more concerns raised about high levels of fluoride exposure and potential links to other conditions. For example, a 2024 U.S. National Toxicology Program (NTP) monograph suggests a potential link between high fluoride levels (above 1.5 mg per liter, more than double the USPHS recommended amounts for community water fluoridation) and lower IQ in children, but studies reviewed for that publication were from areas outside the U.S. with naturally high fluoride concentrations in their water. The monograph concludes that more studies are needed to fully understand the potential for lower levels (under 1.5 mg/L) of fluoride exposure to affect children’s IQ. Based in part on these findings, in September 2024, a US district judge ordered the EPA to take further regulatory action on fluoride, citing the potential risks to children’s neurological development; the EPA says it is reviewing the court decision, but no additional regulatory actions have been taken to date.

Status of Water Fluoridation in the U.S.

As of 2022, the CDC estimates that 72.3% of the U.S. population that is connected to community water systems (CWS) receives fluoridated water, or 62.8% of the U.S. population overall. Not all people are connected to CWS, as a proportion of the population accesses water through wells or other private sources. The overall percentage of the U.S. population with access to fluoridated water has barely changed over the last two decades: in 2006, CDC reported that 61.5% of the population was connected to fluoridated water, compared with 62.8% in 2022. Sometimes, naturally occurring fluoride exists in water systems, and in fact, can be higher than government benchmarks, including maximum recommended levels. According to CDC, as of 2020 about 1 million people in the U.S. (0.31% of the U.S. population) were connected to CWS that had naturally occurring fluoride levels equal to or greater than the EPA’s recommended limit of 2 mg/L.

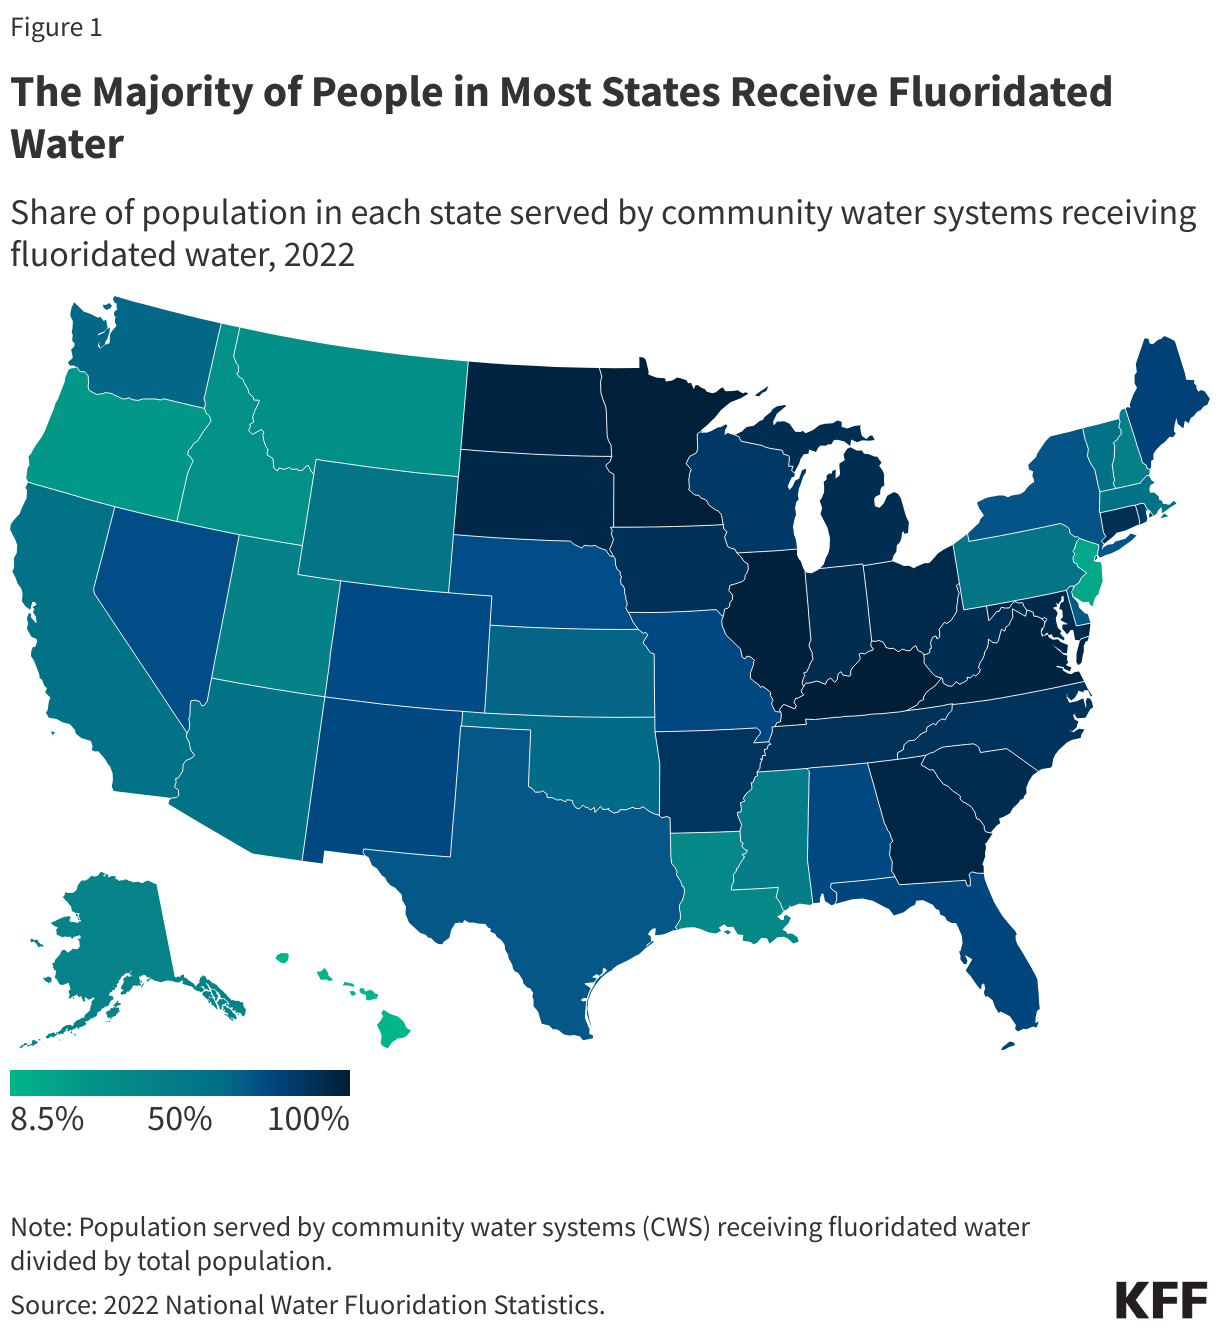
The Majority of People in Most States Receive Fluoridated Water

Access to fluoridated water varies significantly across the country. As of 2022, data from 51 jurisdictions (50 states and Washington, D.C.) show there are seven jurisdictions where over 95% of the population is connected to fluoridated CWS (D.C., Kentucky, Minnesota, Illinois, North Dakota, Virginia, and Georgia) (Figure 1). However, in nine states less than 50% of the population is connected to fluoridated CWS (Hawaii, New Jersey, Oregon, Idaho, Montana, Louisiana, Alaska, Utah, New Hampshire, and Mississippi). These data largely reflect state and local statutes and regulations on fluoridation. Some states require fluoridation for communities above a certain population (including Kentucky, Minnesota, and Illinois), and have relatively high fluoridation rates as a result. Other states leave these decisions up to localities, many of which have decided not to fluoridate their water supplies. In Hawaii, the state with the lowest fluoridation coverage, no locality fluoridates their water systems (with the exception of military bases). Similarly, In New Jersey and Oregon, the states with the second and third lowest coverage rates, local fluoridation decisions have been contentious. More generally, localities are revisiting existing fluoridation policies and considering ending the practice, which typically has to be voted on by water supply recipients.

Rural areas and smaller communities are less likely to have access to fluoridated drinking water. People who live in rural areas are more likely to rely on private wells, which are not usually treated with fluoride, as opposed to public treated water systems. Additionally, smaller communities may face financial barriers that limit their ability to adequately treat their CWSs, decreasing access to fluoridated water for their residents.

VOLUME 12

News Influencers, Opioid Disparities, and AI Bias in Healthcare

This is Irving Washington and Hagere Yilma. We direct KFF’s Health Misinformation and Trust Initiative and on behalf of all of our colleagues across KFF who work on misinformation and trust we are pleased to bring you this edition of our bi-weekly Monitor.


Summary

This volume examines the role of news influencers in spreading misinformation to younger and polarized audiences, as well as misleading narratives about harm reduction amid disparities in opioid overdose rates affecting Black and Indigenous Americans. It also explores biases in artificial intelligence (AI) in healthcare and considerations for improving engagement with health information among marginalized communities and older adults.


Recent Developments

Generational and Political Differences in Accessing Reliable Health News: The Role of News Influencers

izusek / Getty Images

A Pew Research Center poll found a shift in how Americans consume news, with 21% regularly turning to social media influencers for updates. These news influencers are primarily independent content creators with large followings, some of whom are journalists, who post about current events and civic issues on social media platforms. However, this shift toward influencer-based news may raise serious questions about the quality and accuracy of health information reaching the public. While some influencers provide credible insights, others spread false or misleading health claims. Even some influencers with medical credentials included in the sample study by Pew have spread false information about health topics like COVID-19. Other news influencers also contributed to the spread of health misinformation. For example, Joe Rogan, included in Pew’s sample of news influencers, has been criticized for using his platform to amplify false or misleading health information, including AIDS denialism and false claims about vaccine safety.

News influencers’ social media profiles can also be tied to their political ideologies, further complicating the landscape of health information. The Pew analysis found that most news influencers identify with certain political leanings, with right-leaning influencers outnumbering left-leaning influencers on most platforms. Among those who get news from influencers, conservative Republicans and liberal Democrats are more likely than moderate Republicans and Democrats to feel that the content they receive from influencers aligns with their own views. This dynamic can lead to a reinforced echo chamber, where followers consume information that supports their existing beliefs. Political figures who become influencers further complicate the landscape by blending their personal brands with their political roles, and using social media to promote their ideologies. Pew’s sample of news influencers included Mike Huckabee, former Arkansas Governor and nomination for U.S. Ambassador to Israel under the new Trump administration. Huckabee has used his social media platform to comment on health policy, including sharing misleading claims, such as equating abortions later in pregnancy with infanticide.

Addressing Misinformation About Naloxone as Opioid Overdose Remains High Among Black and Indigenous Americans 

Grace Cary / Getty Images

Although opioid deaths declined in 2023, a KFF analysis found disparities across race and ethnicity, with American Indian/Alaska Native (AIAN) and Black communities experiencing the highest rates of drug overdose deaths. Although opioid death rates began to show signs of decline across several demographic groups by 2023, the high vulnerability of AIAN and Black populations persists, reflecting broader systemic challenges, including limited access to treatment and harm reduction resources. Prior to naloxone becoming more widely available, research suggested that compared to White people, Black people had limited access to naloxone, a lifesaving drug that reverses opioid overdoses. Misinformation and stigma about naloxone may contribute to this disparity, such as the incorrect belief that naloxone leads to increased substance use. Fear of police harassment for carrying naloxone or being accused of drug possession can also deter people from accessing or using the drug, especially given the intersection of criminalization and substance use. Some public health campaigns aim to raise awareness about naloxone, but it is unclear whether these efforts are reaching or being received by Black and Indigenous communities. Addressing these issues along with affordability concerns may help address the lack of equitable access to naloxone.

Unsubstantiated Claims About Harm Reduction Programs Fuel Stigma

Cappi Thompson / Getty Images

False claims that harm reduction strategies promote drug use continue to surface in response to news about these programs, even when the news is positive. Harm reduction for opioids can involve various strategies to mitigate risks among users, such as syringe needle distribution and distribution of opioid overdose medications. For example, on November 14, NPR published an article about vending machines that provide free harm reduction tools like naloxone to anyone and sterile syringes to harm reduction clinic clients with a special code, explaining how these tools can help prevent overdose deaths and reduce the spread of infectious diseases. The article also prebunked false claims that harm reduction strategies may increase drug use and crime. Despite sharing this encouraging evidence, several Facebook users responded to NPR’s article with the false claim that harm reduction strategies promote drug use.

Recent misleading claims about harm reduction strategies have also come from public health officials. On October 16, two former top officials at the Department of Health and Human Services published an op-ed on Fox News claiming that the current administration’s harm-reduction strategies have “produced more harm, not less.” The authors claimed that harm reduction strategies promote “acceptance of a drug-using lifestyle.” On the day the article was published, Robert F. Kennedy Jr. shared it on X, stating, “Agreed. To end the opioid crisis we need common sense solutions not ‘harm reduction.’” Most comments agreed with the op-ed, with some falsely claiming that harm reduction strategies provide people with illegal drugs. The article continued to spread on social media platforms, where many posts and comments advocated against harm reduction, falsely claiming that harm reduction can “promote” drug use and discourage treatment.

Despite research showing that harm reduction strategies can prevent overdose deaths, reduce the spread of infectious diseases, and do not increase drug use or crime, the false claim that harm reduction promotes drug use persists. This may reveal public confusion about the goals and functions of harm reduction principles and programs, which aim to reduce the negative effects of drug use and link people to treatment if and when they are ready. Stigmatizing attitudes toward people who use drugs also suggest that the public may not understand that substance use disorder (SUD) is a chronic health condition and although some people are more at risk for it, SUD is fairly common, as nearly three in 10 U.S. adults say they or someone in their family has experienced opioid addiction.


AI & Emerging Technology

Addressing Racial Bias in AI used for Health Care

everythingpossible / Getty Images

Artificial intelligence (AI) is increasingly used in U.S. healthcare, but algorithms often embed racial and ethnic biases that perpetuate disparities in health outcomes. For example, algorithms used to predict health outcomes may inaccurately assess risks for minority groups due to underrepresentation in the training data. Research shows that AI systems often rely on data that overlooks factors such as a patient’s socioeconomic conditions (e.g., access to transportation or healthy food), leading to inaccurate treatment recommendations or misunderstandings about a patient’s ability to follow medical advice. Studies have also found that AI chatbots can share false medical myths about patients of color. Biases in AI systems are further exacerbated by historical inequities and a lack of transparency. Researchers suggest that reforms should focus on increasing diversity in clinical trials, incorporating socio-environmental factors into health care, and improving equity in algorithm development.

Polling Insight:

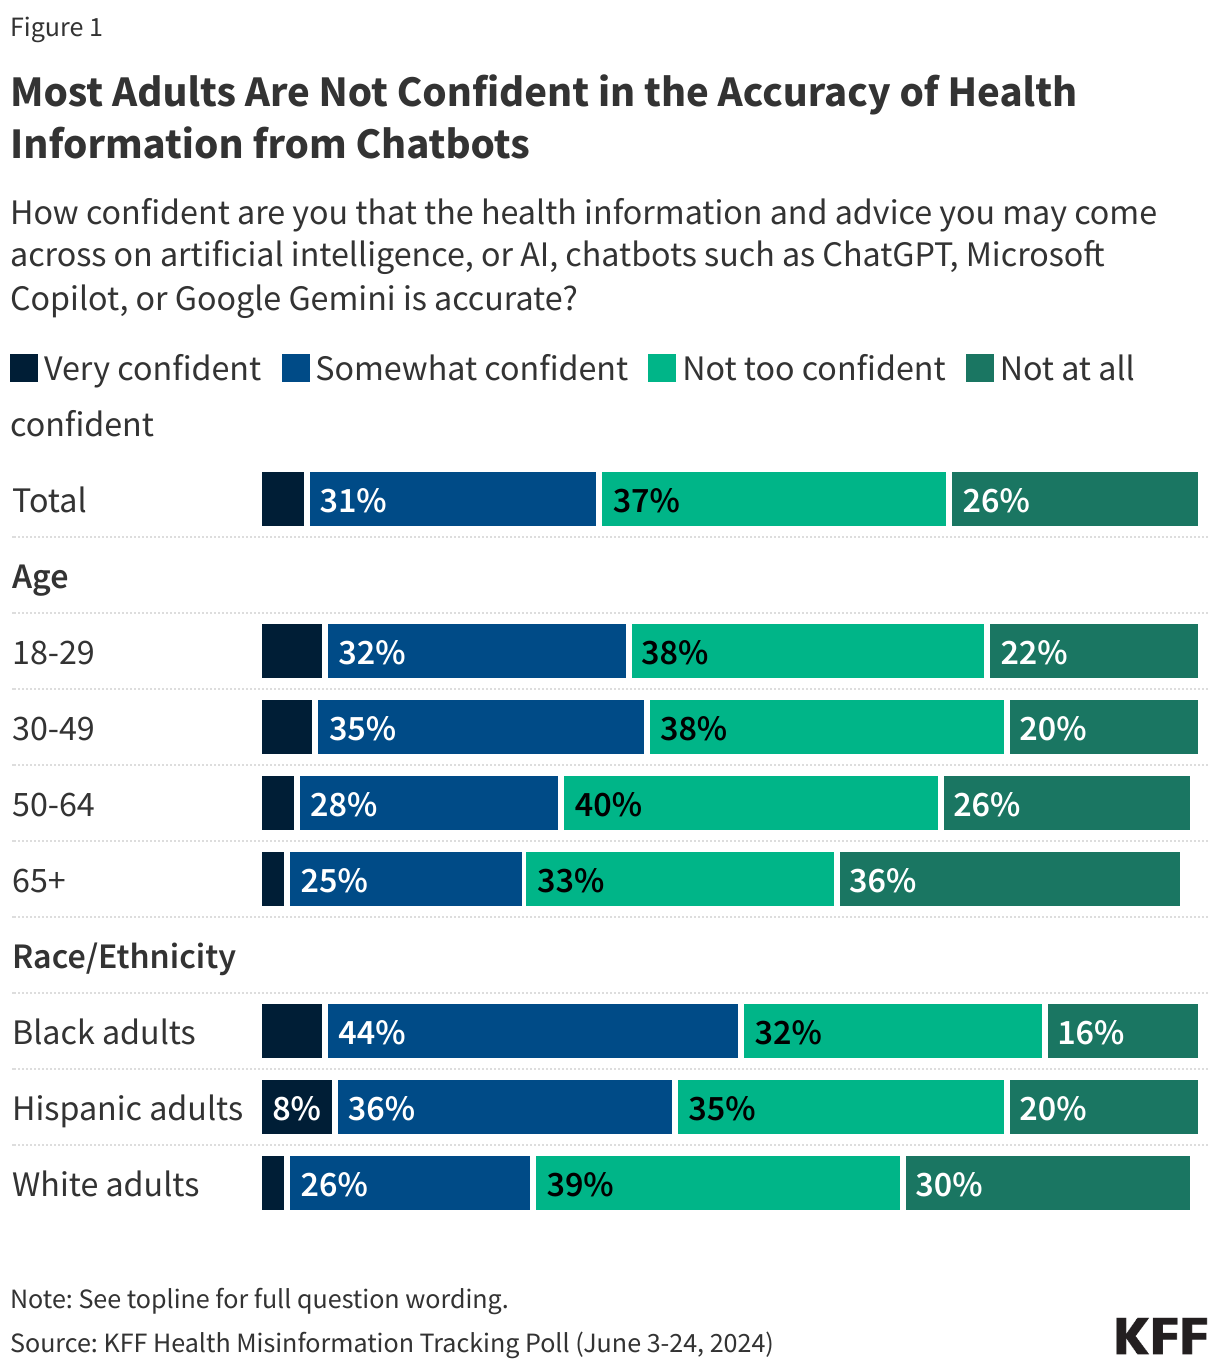
When it comes to health information, the public is not yet convinced that AI chatbots can provide accurate information. KFF’s June Health Misinformation Tracking Poll found that just one in three adults say they are “very confident” (5%) or “somewhat confident (31%) that the health information and advice they may come across on AI chatbot platforms is accurate (Figure 1). About six in ten adults say they are “not too confident” or “not at all confident.”

Notably, adults under age 50 and Black and Hispanic adults are somewhat more likely than those over age 50 and White adults, respectively, to say they have confidence in the accuracy of health information from AI chatbots, though about half or more across age and racial and ethnic groups say they are not confident.

Most Adults Are Not Confident in the Accuracy of Health Information from Chatbots 

Research Insights

Systemic Inequities and Resulting Distrust Make It Difficult for Marginalized Communities to Navigate Science Misinformation

FG Trade / Getty Images

A study published last year in Science Communication conducted focus groups of Black and Latino adults in Boston, MA to understand how historically excluded and marginalized populations perceive science-related issues and engage with misinformation. Participants expressed distrust of authority figures, celebrity endorsements, and fact-checking efforts. Many cited challenges in accessing accurate information due to institutional biases and systemic inequalities, such as discriminatory media algorithms and lack of representation in traditional newsrooms. Participants resonated most with health and wellness topics, especially messages that used storytelling, cultural figures, or social media as a guide. The findings suggest a need for culturally sensitive strategies, including leveraging trusted local leaders and improving access to multilingual, community-specific information to combat misinformation effectively.

Source: Amazeen, M. A., Vasquez, R. A., Krishna, A., Ji, Y. G., Su, C. C., & Cummings, J. J. (2024). Missing voices: examining how misinformation-susceptible individuals from underrepresented communities engage, perceive, and combat science misinformation. Science Communication, 46(1), 3-35.

Sharing Diverse Health Information and Mindfulness Techniques May Combat Information Fatigue in Older Adults

The Good Brigade / Getty Images

A study in Frontiers in Psychology examined how algorithm-driven content may contribute to information overload and avoidance in older adults. Because algorithms often prioritize similar or excessive information, older adults may become fatigued and avoid engaging with health content. The study suggests that mindfulness, the practice of staying focused and non-judgmental, may help mitigate this effect. While mindfulness does not directly reduce fatigue from information overload, it helps individuals engage more effectively with health information. The findings highlight the importance of providing diverse, accessible health content and incorporating mindfulness techniques to improve how older adults process and respond to health-related information.

Source: Zhong, F., & Gu, C. (2024). The impact of health information echo chambers on older adults avoidance behavior: the mediating role of information fatigue and the moderating role of trait mindfulness. Frontiers in Psychology, 15, 1412515.

About The Health Information and Trust Initiative: the Health Information and Trust Initiative is a KFF program aimed at tracking health misinformation in the U.S., analyzing its impact on the American people, and mobilizing media to address the problem. Our goal is to be of service to everyone working on health misinformation, strengthen efforts to counter misinformation, and build trust. 


View all KFF Monitors

The Monitor is a report from KFF’s Health Information and Trust initiative that focuses on recent developments in health information. It’s free and published twice a month.

Sign up to receive KFF Monitor
email updates


Support for the Health Information and Trust initiative is provided by the Robert Wood Johnson Foundation (RWJF). The views expressed do not necessarily reflect the views of RWJF and KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities. The Public Good Projects (PGP) provides media monitoring data KFF uses in producing the Monitor.

Donor Government Funding for Family Planning in 2023

Authors: Adam Wexler, Jennifer Kates, Stephanie Oum, and Eric Lief
Published: Dec 12, 2024

This report provides an analysis of donor government funding for family planning in low- and middle-income countries in 2023, the most recent year available, as well as trends over time. It includes both bilateral funding from donor governments and their contributions to the United Nations Population Fund (UNFPA). It is part of an effort by KFF to track such funding that began after the London Summit on Family Planning in 2012. Overall, donor government funding for family planning increased in 2023, returning to prior year levels, but still below its peak in 2019.

Key findings include the following:

  • Family planning funding from donor governments was US$1.47 billion in 2023. Most funding is provided bilaterally (US$1.4 billion or 95%). The remainder – US$69.6 million (5%) – is for multilateral contributions to UNFPA’s core resources, adjusted for an estimated family planning share.
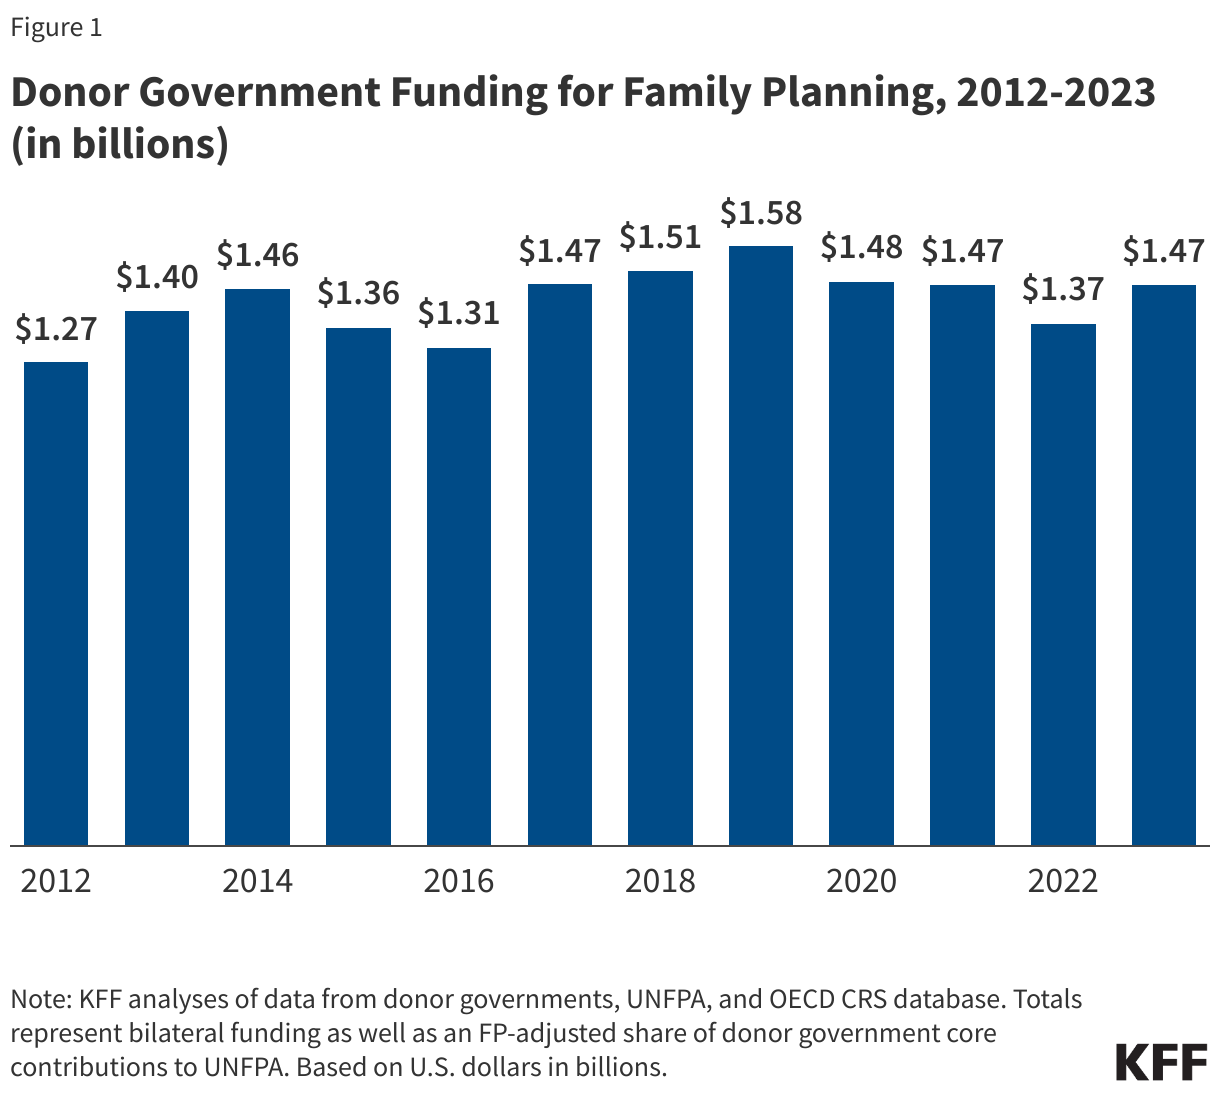
  • This represents an increase of 7% (US$101.1 million) in 2023 compared to US$1.37 billion in 2022 and is a return to prior year levels, but still below its peak reached in 2019 (US$1.58 billion).1 
  • The overall increase was due to increased bilateral funding from most donor governments; multilateral funding (contributions to UNFPA’s core resources) declined slightly largely due to decreases by Germany, Sweden, and the U.S.2 
  • Total funding increased from five donor governments in 2023 (Canada, Germany, the Netherlands, Norway, and the U.K.).3  Funding from the U.S. remained flat, and three countries decreased – Australia, Denmark, and Sweden.4  These trends were the same after accounting for exchange rate fluctuations, except for Sweden, which increased in currency of origin.5 
  • The U.S. continued to be the largest donor to family planning in 2023, accounting for 40% (US$582.5 million) of total funding from governments, followed by the Netherlands (US$246.5 million, 17%), the U.K. (US$198.6 million, 13%), Sweden (US$124.5 million, 8%) and Canada (US$112.2 million, 8%). However, when family planning funding is standardized by the size of donor economies, the Netherlands ranked first, followed by Sweden, and Norway; the U.S. ranked 7th.

The future of donor government support for family planning, however, is uncertain. A second Trump administration will almost certainly see an end to U.S. support for UNFPA, and proposed cuts to bilateral funding, as was seen in his first term. Moreover, the extent to which other donors will fill in any gaps created by the U.S. is unclear, as they face their own financial pressures and changes in leadership. Such uncertainties, and potential funding reductions, would create new challenges for reaching people in low- and middle-income countries with family planning services.

Introduction

This report provides data on donor government funding for family planning activities in low- and middle-income countries in 2023, the most recent year available, as well as trends over time. It is part of an effort by KFF that began after the London Summit on Family Planning in 2012 and includes data from all 32 members of the Organisation for Economic Co-operation and Development (OECD)’s Development Assistance Committee (DAC). Data are collected directly from the largest donors and supplemented with data from the DAC. Direct data collection was carried out for nine donor governments that account for 97% of total funding for family planning. Both bilateral assistance and core contributions to UNFPA, adjusted for a family planning share, are included. For more detail, see methodology.

Findings

Total Funding

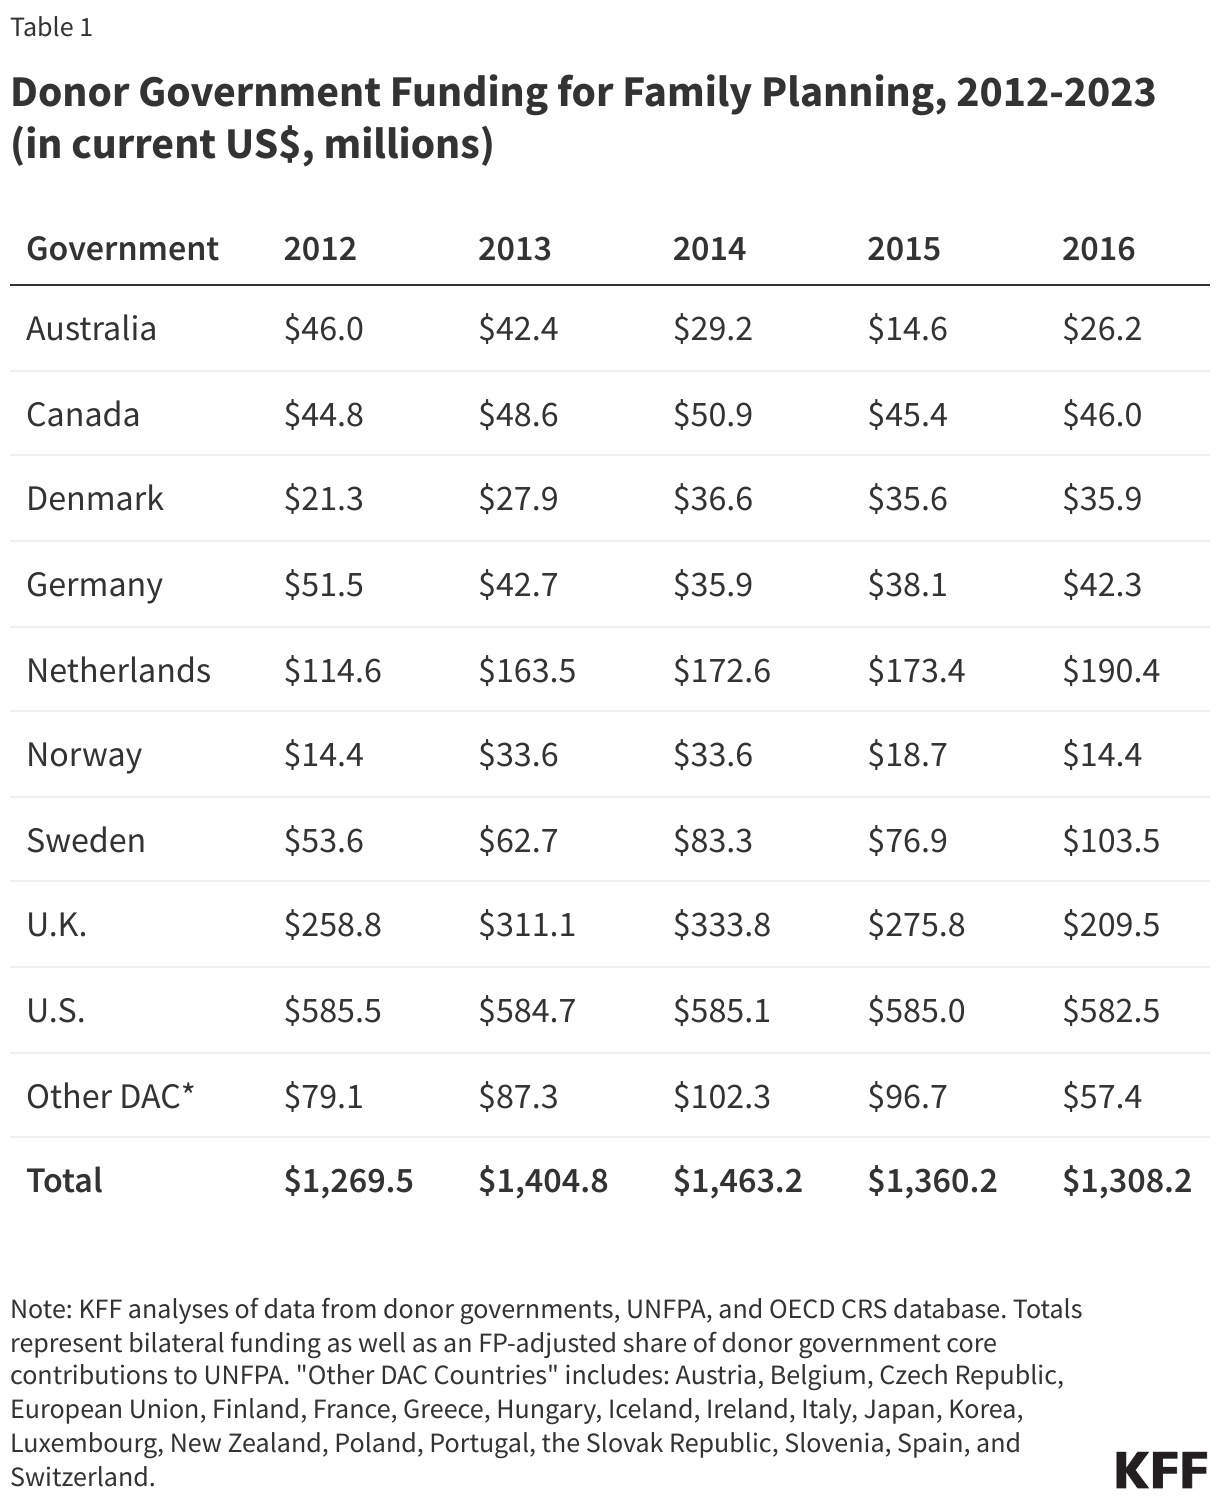
In 2023, donor government funding for family planning through bilateral and multilateral channels totaled US$1.47 billion, an increase of US$101.1 million, or 7%, compared to 2022 (US$1.37 billion). While this marks a return to prior year levels, it is below the peak level reached in 2019 (US$1.58 billion) (see Figure 1 & Table 1). The increase was entirely due to increased bilateral support from the majority of donor governments; multilateral funding decreased slightly (see “Bilateral Funding” and “Multilateral Funding” sections below).

Donor Government Funding for Family Planning, 2012-2023 (in billions)

Total funding increased from five donor governments in 2023 (Canada, Germany, the Netherlands, Norway, and the U.K.).6  Funding from the U.S. remained flat, and three countries decreased – Australia, Denmark, and Sweden.7 ,8  These trends were the same after accounting for exchange rate fluctuations, except for Sweden, which increased in currency of origin.9  There were, however, some differences among the donor governments in the amount of bilateral and multilateral funding provided between 2022 and 2023 (see Bilateral and Multilateral sections below).

Donor Government Funding for Family Planning, 2012-2023 (in current US$, millions)

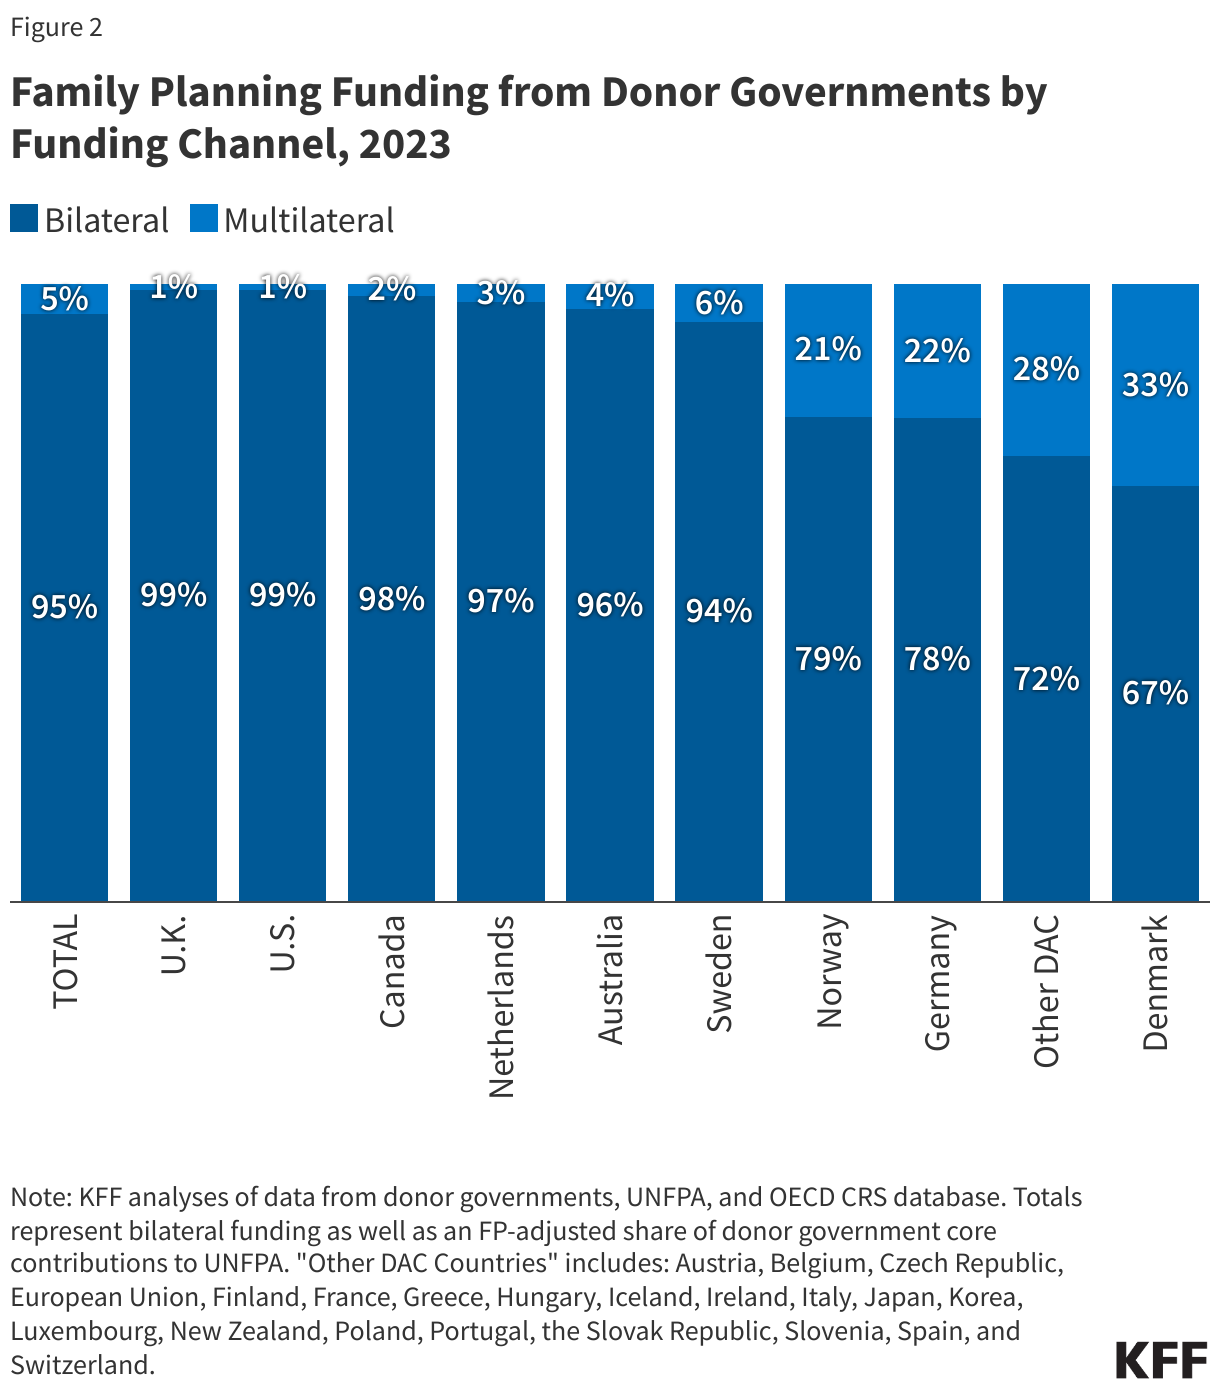
The vast majority of donor government funding for family planning is provided bilaterally (95%). The remainder (5%) is for multilateral contributions to UNFPA’s core resources, adjusted based on the share used to support family planning activities. All donor governments provided a larger share of their family planning funding bilaterally (see Figure 2).

Family Planning Funding from Donor Governments by Funding Channel, 2023

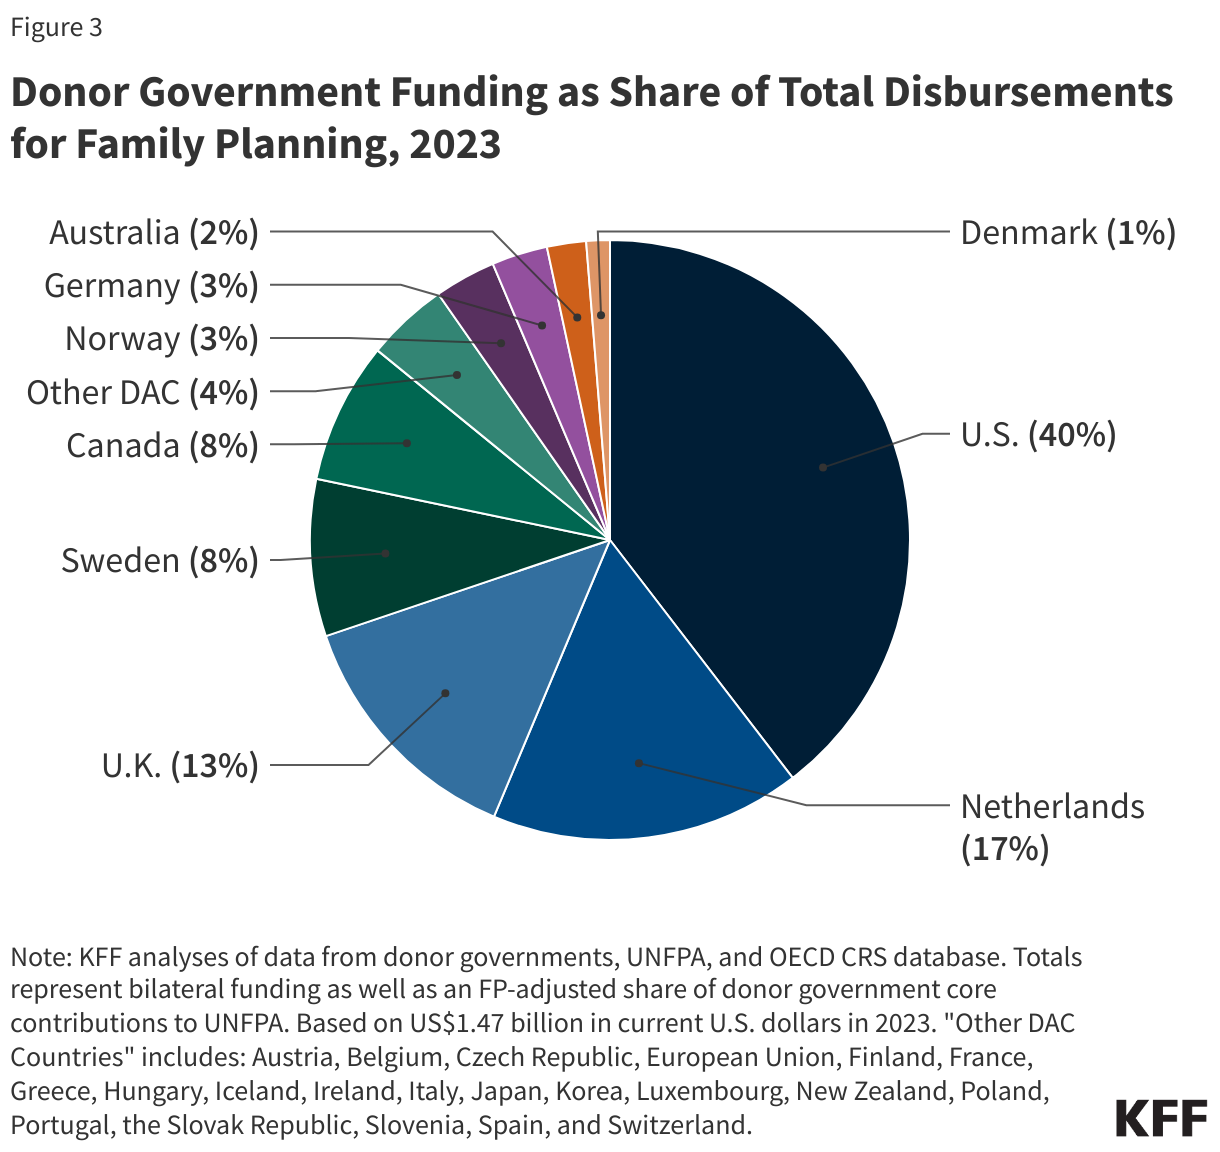
The U.S. continued to be the largest government donor to family planning in 2023, accounting for 40% (US$582.5 million) of total donor government funding (see Figure 3). The Netherlands was the second largest donor (US$246.5 million or 17%), followed by the U.K. (US$198.6 million or 13%), and Sweden (US$124.5 million or 8%).

Donor Government Funding as Share of Total Disbursements for Family Planning, 2023

Bilateral Funding

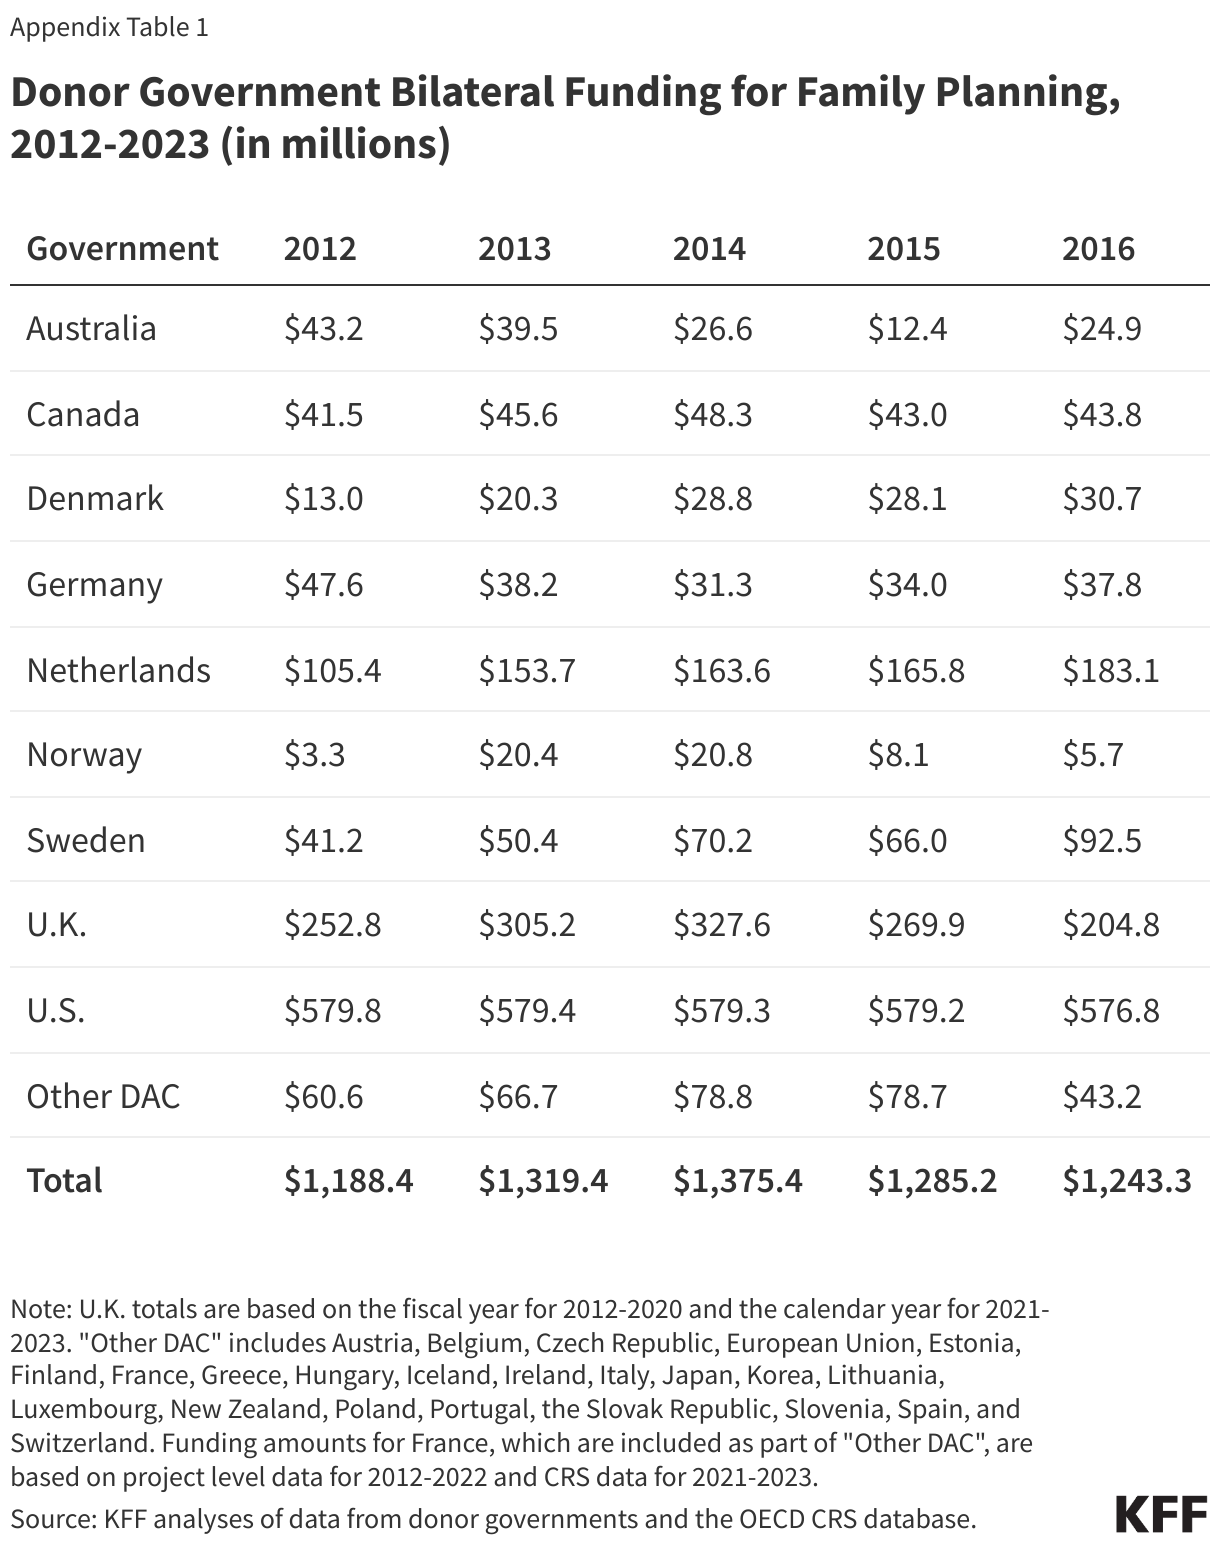
Bilateral disbursements for family planning from donor governments – that is, funding disbursed by a donor on behalf of a recipient country or region – totaled US$1.40 billion in 2023, an increase of US$111.2 million, or 9%, compared to 2022 (US$1.29 billion) (see Appendix Table 1).

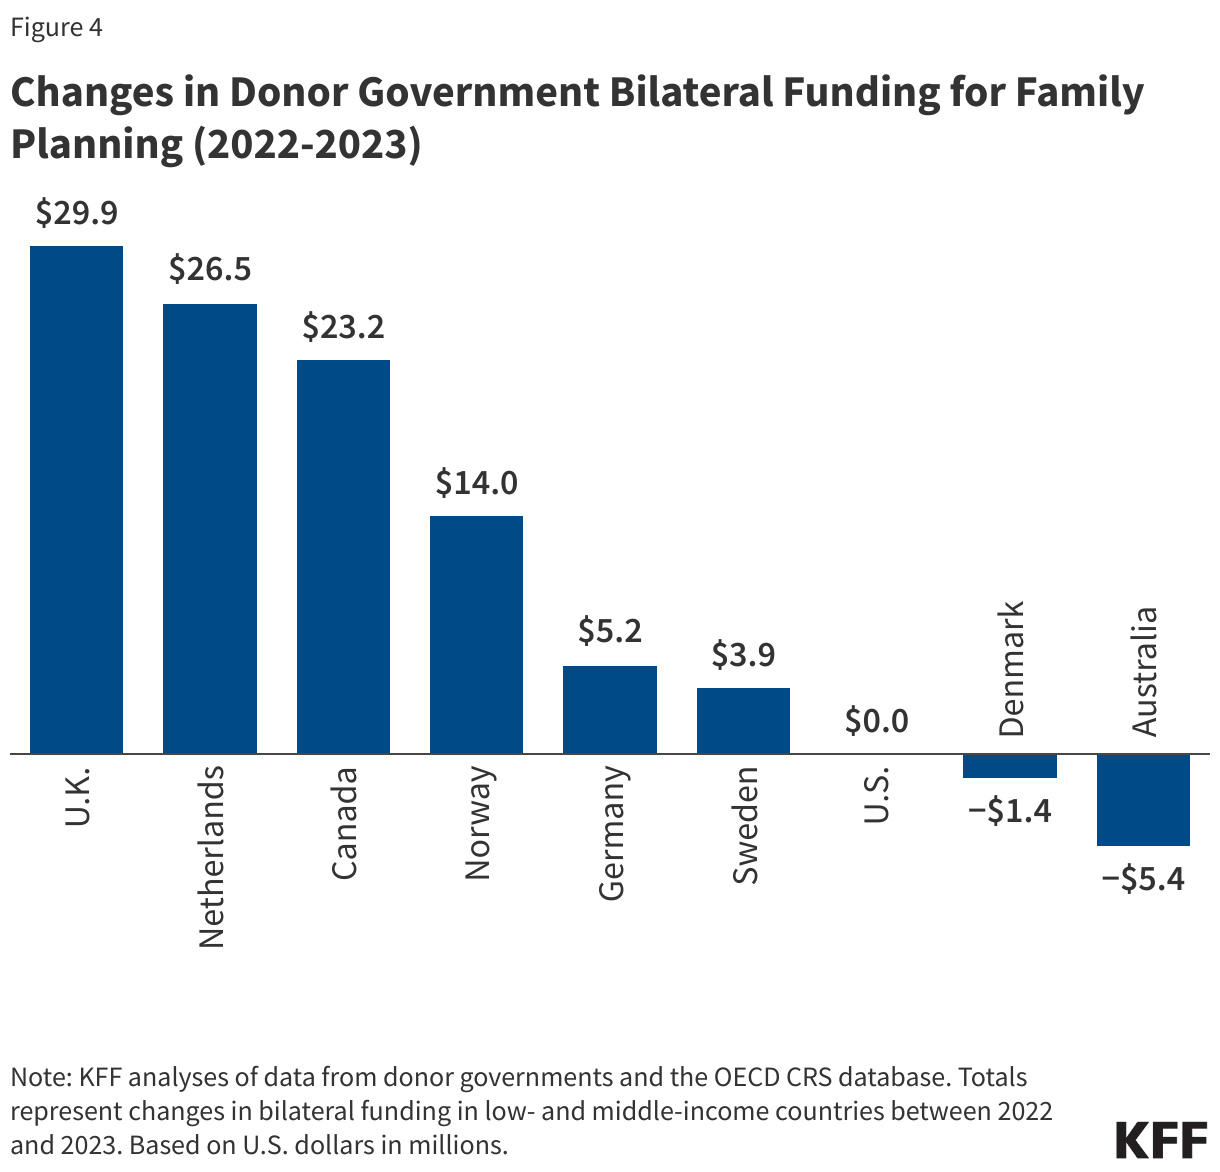
Bilateral funding from six donor governments (Canada, Germany, the Netherlands, Norway, Sweden, and the U.K.) increased in 2023 (see Figure 4).10  Two donor governments (Australia and Denmark) decreased funding in 2023, while the U.S. remained flat. These trends were the same after accounting for exchange rate fluctuations.

Changes in Donor Government Bilateral Funding for Family Planning (2022-2023)

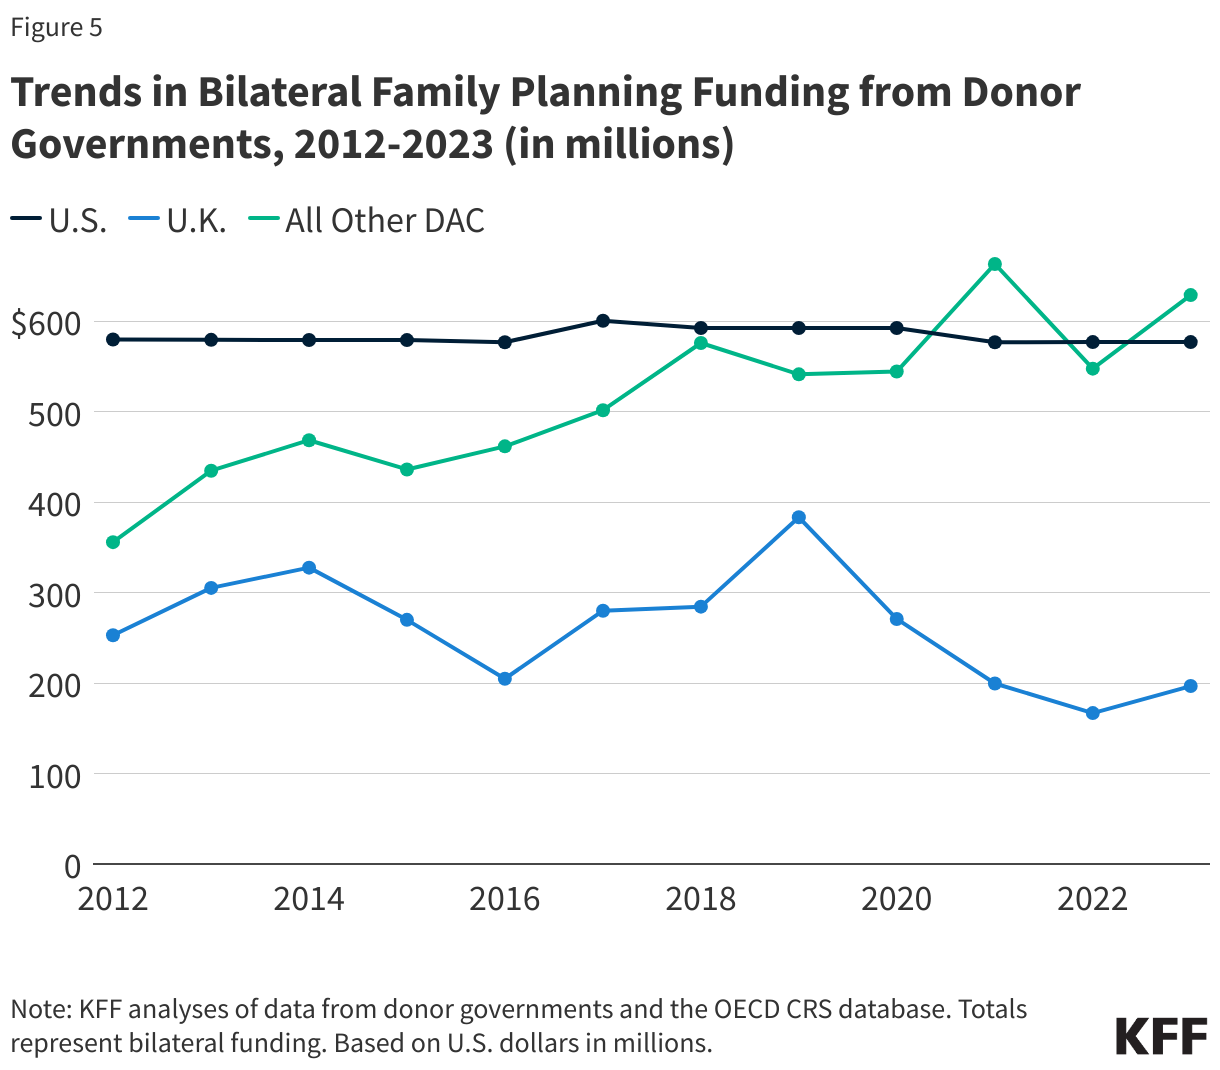
The U.S. and U.K. have been the top two donors over the entire period since the London Summit (2012-2023). However, U.S. funding has been relatively flat while funding from the U.K., which fluctuated over the period, has declined in recent years. When these two are removed, bilateral funding from the other donor governments has generally increased over the period; although, there have been fluctuations (see Figure 5).

Trends in Bilateral Family Planning Funding from Donor Governments, 2012-2023 (in millions)

Multilateral Funding

While the majority of donor government assistance for family planning is provided bilaterally, donors also provide support for family planning activities through core contributions to the United Nations Population Fund (UNFPA) (where donors direct or earmark funding for specific family planning activities, such as for UNFPA Supplies, these are included as part of bilateral funding). In 2023, UNFPA estimates that 18% of its core funding was directed to family planning activities.11 

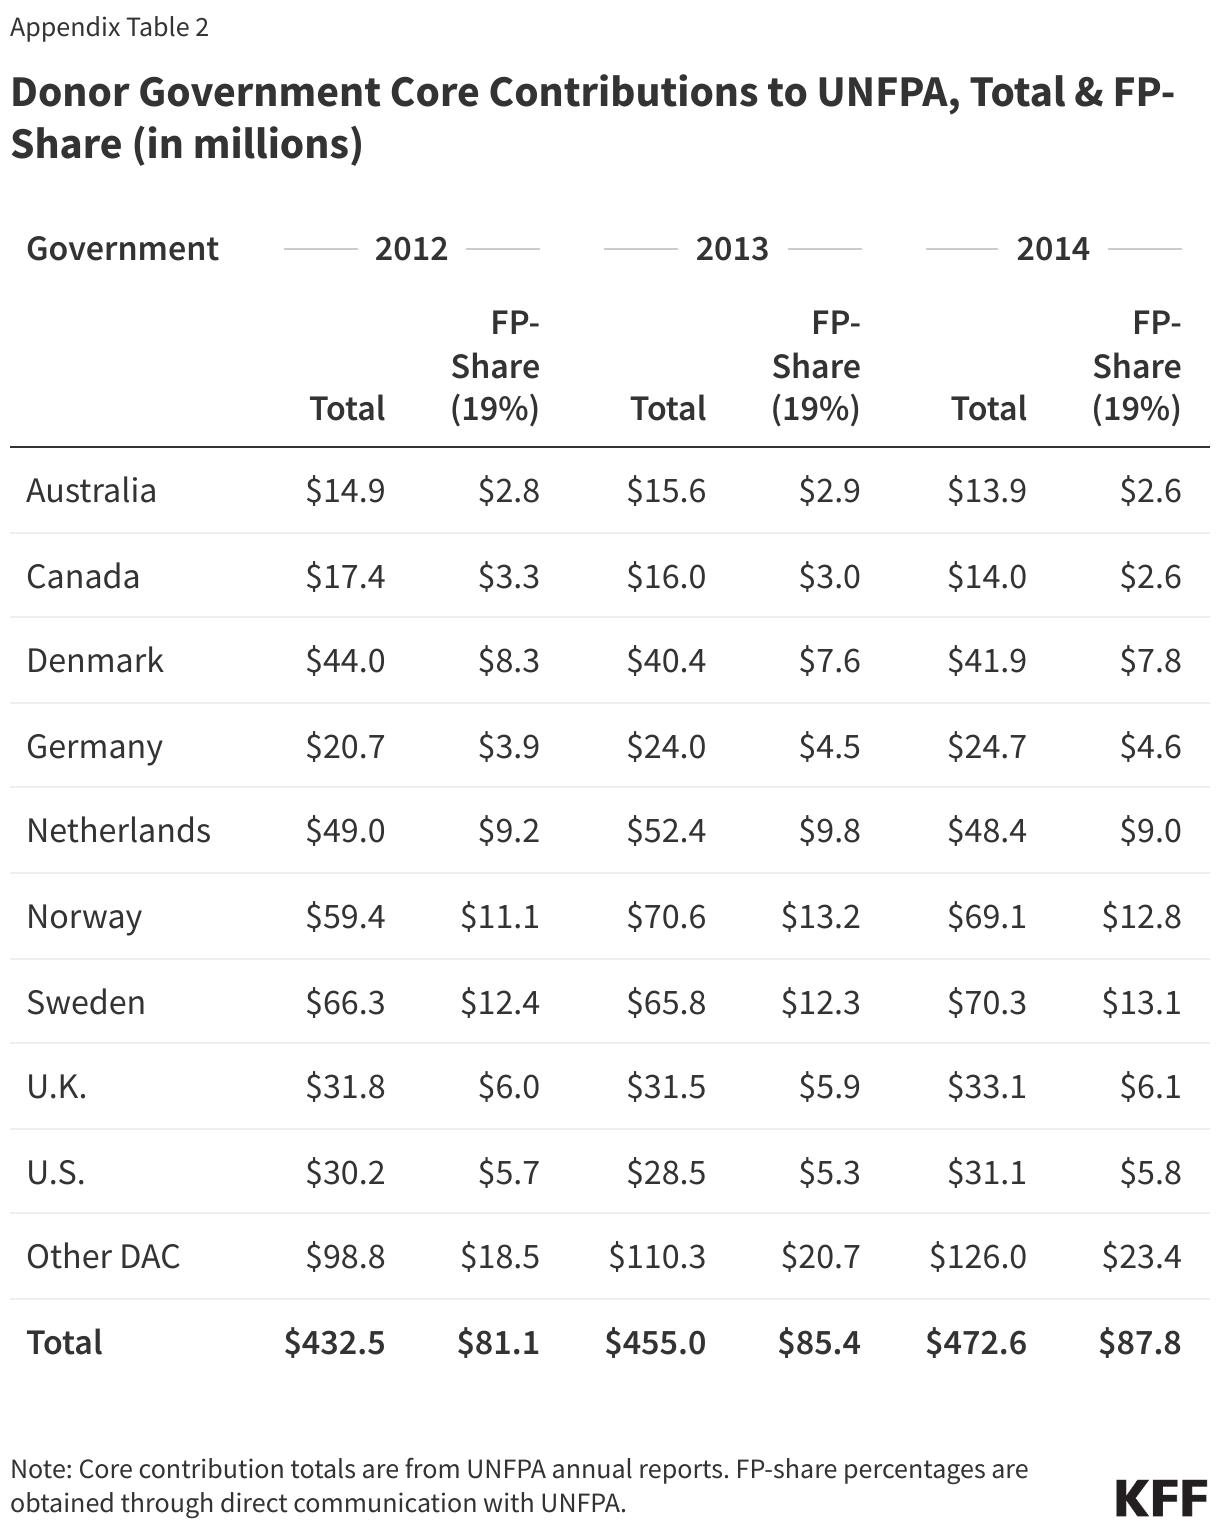
These totaled US$69.6 million in 2023, a decrease of US$10.1 million compared to 2022 (US$79.7 million) (see Appendix Table 2). The decrease was entirely due to a decline in total contributions to UNFPA’s core resources – largely from Germany, Sweden, and the U.S, rather than a change in the share of core resources UNFPA directed to family planning activities.12 ,13  Norway was the largest donor government to UNFPA’s core resources, followed by Germany, Sweden, and the Netherlands.

Fair Share

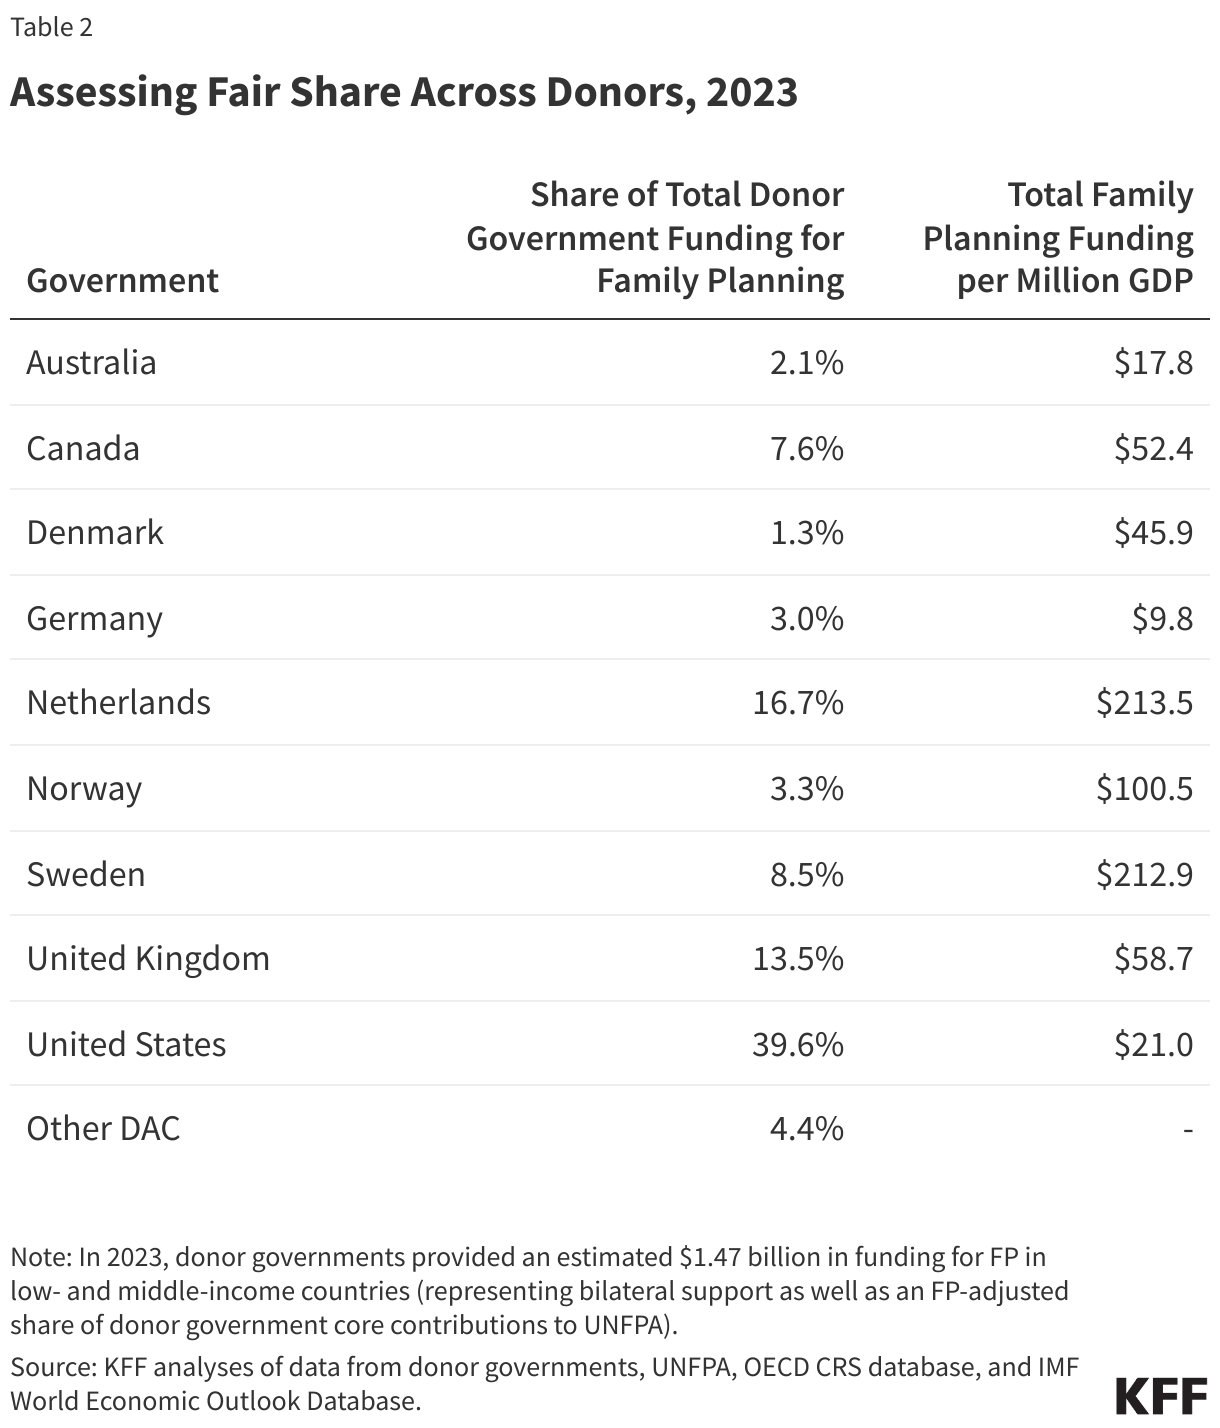
We looked at two different measures to assess the relative contributions of donor governments, or “fair share”, to family planning (see Table 2) as follows: rank by share of total donor government disbursements for family planning, and rank by funding for family planning per US$1 million in gross domestic product (GDP).

  • Rank by share of total donor government funding for family planning: By this measure, the U.S. ranked first in 2022, followed by the Netherlands, the U.K., Sweden, and Canada. The U.S. has consistently ranked #1 in absolute funding amounts over the entire period since the London Summit (2012-2023).
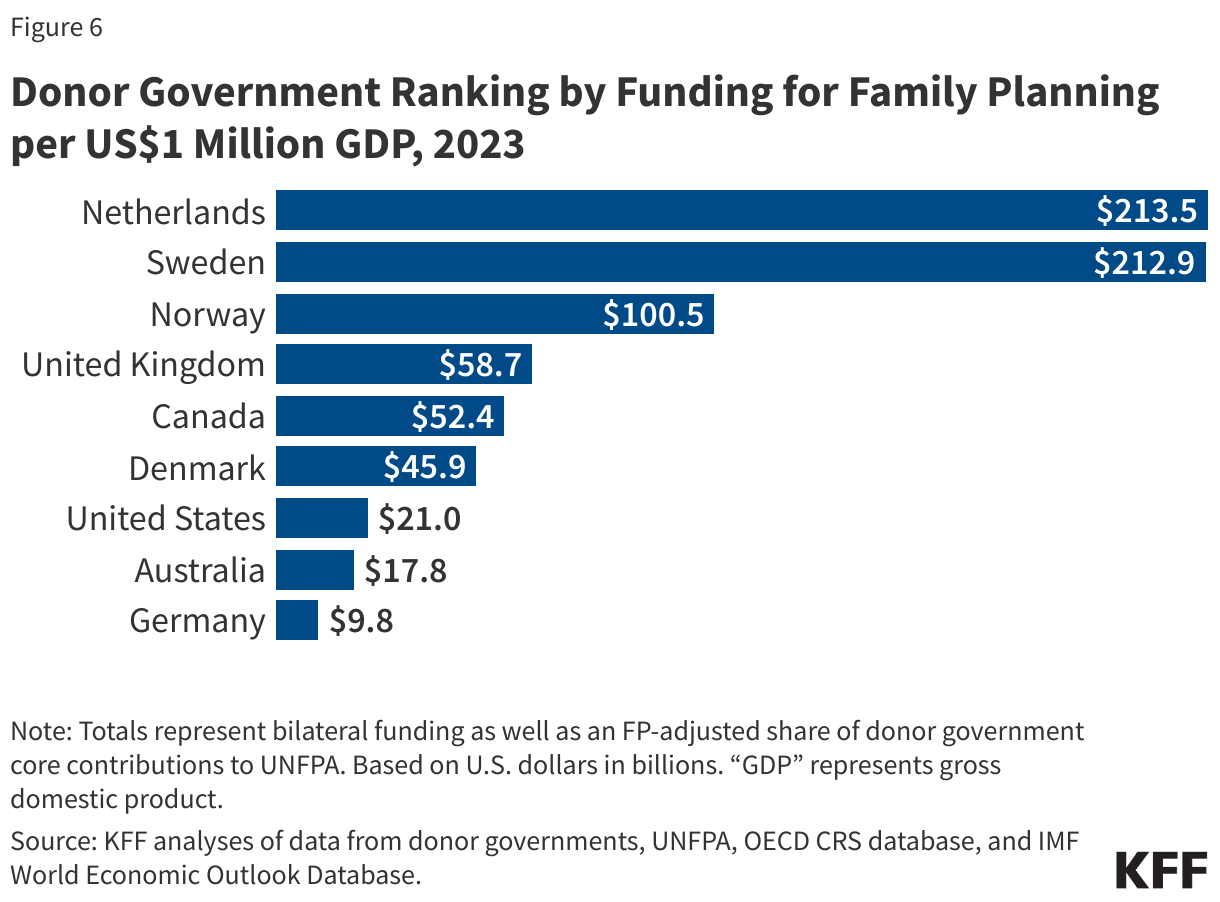
  • Rank by funding for family planning per US$1 million GDP: When funding for family planning is standardized by the size of donor economies (GDP per US$1 million), the Netherlands ranks at the top, followed by Sweden, Norway, and the U.K. (Figure 6); the U.S. ranks 7th.
Assessing Fair Share Across Donors, 2023
Donor Government Ranking by Funding for Family Planning per US$1 Million GDP, 2023

This work was supported in part by the Bill & Melinda Gates Foundation. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

Adam Wexler, Jen Kates, and Stephanie Oum are with KFF. Eric Lief is an independent consultant.

Methods

Totals presented in this analysis include both bilateral funding for family planning in low- and middle-income countries as well as the estimated share of donor government contributions to UNFPA’s core resources that are used for family planning. Amounts are based on analysis of data from the 32 donor government members of the Organisation for Economic Co-operation and Development (OECD) Development Assistance Committee (DAC) in 2023 who had reported Official Development Assistance (ODA). Bilateral and multilateral data were collected from multiple sources.

Bilateral Funding:

Bilateral funding is defined as any earmarked (family planning designated) amount and includes family planning-specific contributions to multilateral organizations (e.g., non-core contributions to UNFPA Supplies). For purposes of this analysis, funding was counted as family planning if it met the OECD CRS purpose code definition: “Family planning services including counselling; information, education and communication (IEC) activities; delivery of contraceptives; capacity building and training.”

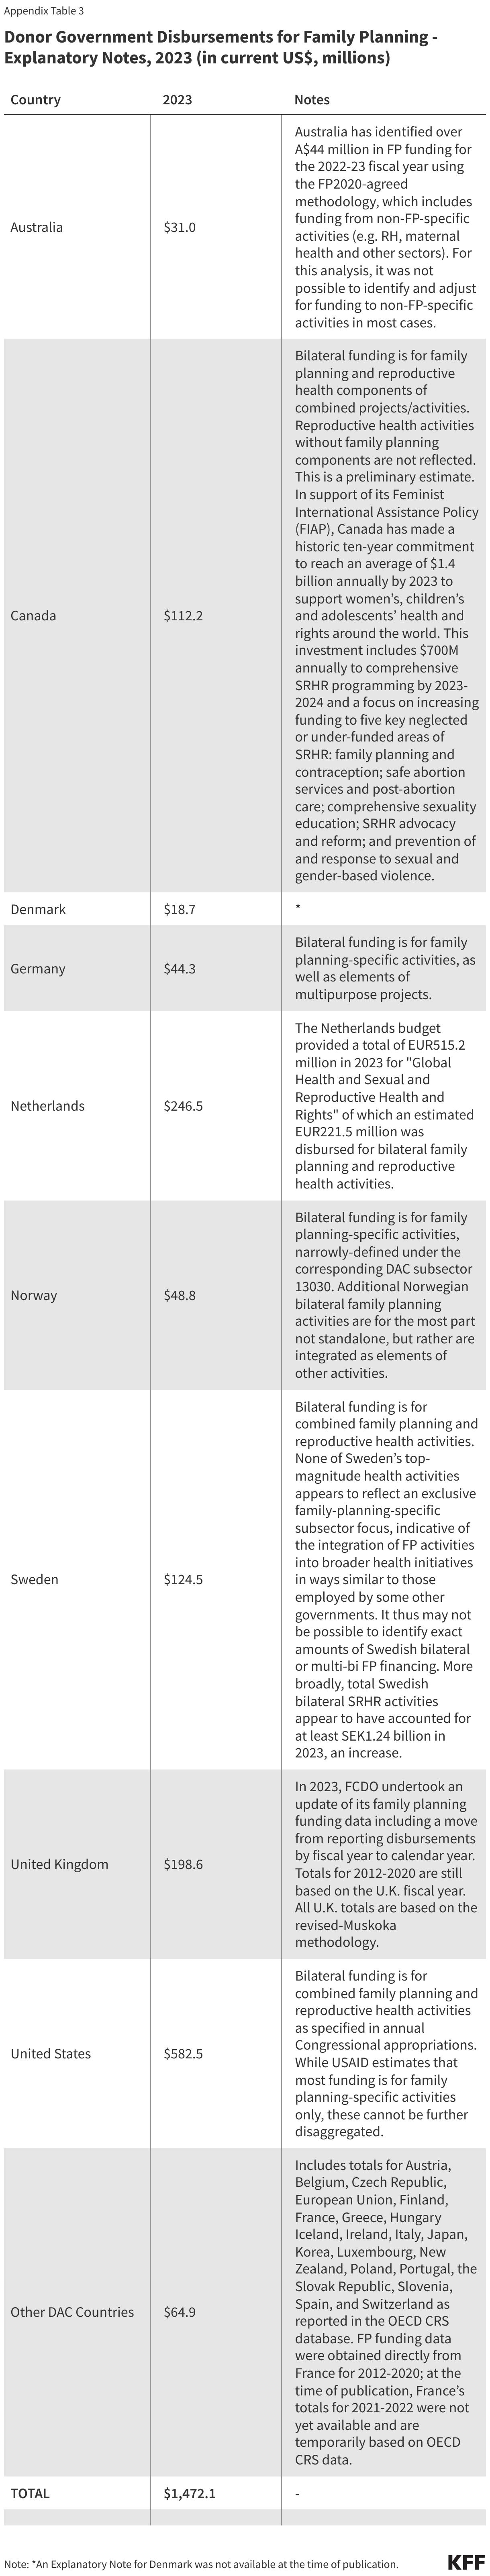
The research team collected the latest bilateral funding data directly from nine governments: Australia, Canada, Denmark, Germany, the Netherlands, Norway, Sweden, the United Kingdom, and the United States during 2023 (see Appendix Table 3). Direct data collection from these donors was desirable because they represent the preponderance of donor government assistance for family planning and the latest official statistics – from the Organisation for Economic Co-operation and Development (OECD) Creditor Reporting System (CRS) (see: http://www.oecd.org/dac/stats/data) – do not include all forms of international assistance (e.g., funding to countries such as Russia and the Baltic States that are no longer included in the CRS database). In addition, the CRS data may not include certain funding streams, such as family planning components of mixed-purpose grants to non-governmental organizations, provided by donors. Data for all other OECD DAC member governments – Austria, Belgium, Czech Republic, the European Union, Estonia, Finland, France, Greece, Hungary, Iceland, Ireland, Italy, Japan, Korea, Lithuania, Luxembourg, New Zealand, Poland, Portugal, the Slovak Republic, Slovenia, Spain, and Switzerland – which collectively accounted for approximately 3 percent of bilateral family planning disbursements, were obtained from the OECD CRS database and are from 2022 calendar year.

For some donor governments, it was difficult to disaggregate bilateral family planning funding from broader population, reproductive and maternal health totals, as the two are sometimes represented as integrated totals. In other cases, funding for family-planning-related activities provided in the context of other official development assistance sectors (e.g., humanitarian assistance, education, civil society) was included if identifiable (e.g., if donors indicate specific family planning percentages for mixed-purpose projects, or if it was possible to identify family planning specific funding based on project titles and/or descriptions).

With some exceptions, bilateral assistance data represent disbursements. A disbursement is the actual release of funds to, or the purchase of goods or services for, a recipient. Disbursements in any given year may include disbursements of funds committed in prior years and in some cases, not all funds committed during a government fiscal year are disbursed in that year. In addition, a disbursement by a government does not necessarily mean that the funds were provided to a country or other intended end-user. Enacted amounts represent budgetary decisions that funding will be provided, regardless of the time at which actual outlays, or disbursements, occur. In recent years, most governments have converted to cash accounting frameworks, and presented budgets for legislative approval accordingly; in such cases, disbursements were used as a proxy for enacted amounts.

Amounts presented are for the fiscal year period, which vary by country. The U.S. fiscal year runs from October 1-September 30. The Australian fiscal year runs from July 1-June 30. The fiscal years for Canada and the U.K. are April 1-March 31. Denmark, Germany, the Netherlands, Norway, and Sweden use the calendar year. The OECD uses the calendar year, so data collected from the CRS for other donor governments reflect January 1-December 31. Most UN agencies use the calendar year, and their budgets are biennial.

All data are expressed in US dollars (USD). Where data were provided by governments in their currencies, they were adjusted by average daily exchange rates to obtain a USD equivalent, based on foreign exchange rate historical data available from the U.S. Federal Reserve (see: http://www.federalreserve.gov/) or in some cases from the OECD. Funding totals presented in this analysis should be considered preliminary estimates based on data provided and validated by representatives of the donor governments who were contacted directly.

Specific notes pertaining to the donor governments where direct data collection was conducted are as follows:

  • Project-level data were reviewed for Canada, Denmark, Germany, the Netherlands, Norway, and Sweden to determine whether all or a portion of the funding could be counted as family planning.
  • Project-level data were also reviewed for France for 2012-2020, but comparable data were not available for 2021-2023, so totals for these years are based on the OECD DAC CRS database. Totals for 2021-2023 will be updated once comparable data become available. Starting with the report presenting 2022 funding amounts, totals for France were included under the amounts presented for all other DAC members; prior reports presented totals for France separately.
  • Funding attributed to Australia and the United Kingdom is based on a revised Muskoka methodology as agreed upon by donors at the London Summit on Family Planning in 2012.
  • For the U.S., funding represents final, Congressional appropriations (firm commitments that will be spent) to the U.S. Agency for International Development (USAID), rather than disbursements, which can fluctuate from year-to-year due to the unique nature of the U.S. budget process (unlike most other donors, U.S. foreign assistance funding may be disbursed over a multi-year period). U.S. totals for 2017-2020 also include some funding originally appropriated by Congress for UNFPA that was transferred to the USAID family planning & reproductive health (FP/RH) account due to specific provisions in U.S. law including the Kemp-Kasten amendment (see KFF “UNFPA Funding & Kemp-Kasten: An Explainer”).

Multilateral Funding:

UNFPA core contributions were obtained from United Nations Executive Board documents and correspond to amounts received during the 2023 calendar year, regardless of which contributor’s fiscal year such disbursements pertain to. Data were already adjusted by UNFPA to represent a USD equivalent based on date of receipts. UNFPA estimates of total family planning funding provided from core resources were obtained through direct communications with UNFPA representatives for 2012-2021; family planning funding estimates from UNFPA’s core resources for 2022-2023 are based on amounts reported on UNFPA’s Transparency Portal and designated as for “Ending the Unmet Need for Family Planning”.

UNFPA’s core resources are meant to be used for both programmatic activities (family planning, population and development, HIV/AIDS, gender, and sexual and reproductive health and rights) as well as operational support. Donor government contributions to UNFPA’s core resources were adjusted to reflect the share of core resources supporting family planning activities in a given year based on information from UNFPA. For instance, in 2023, UNFPA reported expenditures totaling US$500 million from core resources including US$92 million for family planning activities, which results in an estimated 18% of a donor government’s core contribution in 2023 being included in its total funding for family planning.14 ,15 

Other than core contributions provided by governments to UNFPA, un-earmarked core contributions to United Nations entities, most of which are membership contributions set by treaty or other formal agreement (e.g., United Nations country membership assessments), are not identified as part of a donor government’s family planning assistance even if the multilateral organization in turn directs some of these funds to family planning. Rather, these would be considered as family planning funding provided by the multilateral organization and are not included in this report.

Donor Government Bilateral Funding for Family Planning, 2012-2023 (in millions)
Donor Government Core Contributions to UNFPA, Total & FP-Share (in millions)
Donor Government Disbursements for Family Planning - Explanatory Notes, 2023 (in current US$, millions)
  1. Family planning totals are different from those reported last year due to updated data received after the 2023 report was published. Donor amounts do not exactly sum up to total amounts due to rounding. ↩︎
  2. The U.S. decline in its core contribution to UNFPA in 2023 was due to a one-time increase that occurred in the previous year. In 2022, the U.S. core contribution to UNFPA included the direct appropriation (US$30.6 million) provided by Congress as well as a one-time US$20 million contribution provided by the Biden administration through available funding from the American Rescue Plan Act of 2021 (P.L. 117-2). ↩︎
  3. In 2023, the U.K. Foreign, Commonwealth and Development Office (FCDO) undertook an update of its family planning funding data including a move from reporting disbursements by fiscal year to calendar year. Updated data for the entire period were not at the time of publication. As such, U.K. totals for 2021-2023 are based on the calendar year; totals for 2012-2020 are still based on the U.K. fiscal year and will be updated in the next report (overall trends are not expected to change as a result of the forthcoming update). The 2021 and 2022 totals previously reported were considered preliminary estimates and have been revised. All U.K. totals are based on the revised-Muskoka methodology. ↩︎
  4. The assessment that total U.S. family planning funding was flat in 2023 compared to 2022 is based on the amounts specified by the U.S. Congress in annual appropriations bills. The family planning amounts specified by Congress were the same in 2022 and 2023. The U.S. family planning total for 2022 as presented in this report is slightly higher than 2023 due to a one-time additional contribution to UNFPA’s core resources provided by the Biden administration (see Multilateral section). ↩︎
  5. In most cases, donor governments provide funding data in their currency of origin, which are converted to U.S. dollars for this report (see Methods). ↩︎
  6. In 2023, the U.K. Foreign, Commonwealth and Development Office (FCDO) undertook an update of its family planning funding data including a move from reporting disbursements by fiscal year to calendar year. Updated data for the entire period were not at the time of publication. As such, U.K. totals for 2021-2023 are based on the calendar year; totals for 2012-2020 are still based on the U.K. fiscal year and will be updated in the next report (overall trends are not expected to change as a result of the forthcoming update). The 2021 and 2022 totals previously reported were considered preliminary estimates and have been revised. All U.K. totals are based on the revised-Muskoka methodology. ↩︎
  7. The assessment that total U.S. family planning funding was flat in 2023 compared to 2022 is based on the amounts specified by the U.S. Congress in annual appropriations bills. The family planning amounts specified by Congress were the same in 2022 and 2023. The U.S. family planning total for 2022 as presented in this report is slightly higher than 2023 due to a one-time additional contribution to UNFPA’s core resources provided by the Biden administration (see Multilateral section). ↩︎
  8. “Other DAC Countries”, which includes: Austria, Belgium, Czech Republic, European Union, Finland, France, Greece, Hungary, Iceland, Ireland, Italy, Japan, Korea, Luxembourg, New Zealand, Poland, Portugal, the Slovak Republic, Slovenia, Spain, and Switzerland, is not listed under any assessment of increasing, decreasing, or remaining flat because there may be differences among the donor governments included. ↩︎
  9. In most cases, donor governments provide funding data in their currency of origin, which are converted to U.S. dollars for this report (see Methods). ↩︎
  10. “Other DAC Countries”, which includes: Austria, Belgium, Czech Republic, European Union, Finland, France, Greece, Hungary, Iceland, Ireland, Italy, Japan, Korea, Luxembourg, New Zealand, Poland, Portugal, the Slovak Republic, Slovenia, Spain, and Switzerland, is not listed under any assessment of increasing, decreasing, or remaining flat because there may be differences among the donor governments included. ↩︎
  11. The family planning share of UNFPA’s core resources is based on several sources including: expenditure totals as reported in UNFPA’s annual report; family planning expenditure totals as presented on UNFPA’s Programme Expenses Portal (see here), and direct communication with UNFPA (see Methods). ↩︎
  12. The U.S. decline in its core contribution to UNFPA in 2023 was due to a one-time increase that occurred in the previous year. In 2022, the U.S. core contribution to UNFPA included the direct appropriation (US$30.6 million) provided by Congress as well as a one-time US$20 million contribution provided by the Biden administration through available funding from the American Rescue Plan Act of 2021 (P.L. 117-2). ↩︎
  13. “Other DAC Countries”, which includes: Austria, Belgium, Czech Republic, European Union, Finland, France, Greece, Hungary, Iceland, Ireland, Italy, Japan, Korea, Luxembourg, New Zealand, Poland, Portugal, the Slovak Republic, Slovenia, Spain, and Switzerland, is not listed under any assessment of increasing, decreasing, or remaining flat because there may be differences among the donor governments included. ↩︎
  14. UNFPA, “United Nations Population Fund, Statistical and financial review, 2023 - Annexes, Report of the Executive Director”; April, 2024. ↩︎
  15. UNFPA, Transparency Portal (see here); accessed November 2024. ↩︎
News Release

Medicare Spent an Average of 27% More on People Who Switched from Medicare Advantage to Traditional Medicare Compared to Those Who Were Only in Traditional Medicare

Published: Dec 6, 2024

A new KFF analysis finds higher Medicare spending among people who switched from Medicare Advantage to traditional Medicare than for similar beneficiaries who were in traditional Medicare all along.

Medicare spent an average of 27% more on such beneficiaries, according to the analysis, which examined health costs in traditional Medicare for both groups in the year following the switch, after adjusting for differences in health status and other characteristics. This amounts to a difference of $2,585 in Medicare spending per person, on average, between the two groups in 2022. The difference in spending among people with certain health conditions varied from 15% for those with pneumonia to 34% for people with diabetes.  

The higher Medicare spending among beneficiaries who disenrolled from Medicare Advantage compared to similar beneficiaries in traditional Medicare was due to skilled nursing facility spending (34%), followed by outpatient hospital spending (23%), and inpatient hospital spending (20%), with some variation by chronic conditions and other beneficiary characteristics. 

In 2024, more than half of all eligible Medicare beneficiaries were enrolled in a Medicare Advantage plan. Other research has found that people who use relatively more health care services are less likely to sign up for one of the private plans and more likely to choose traditional Medicare.  

The higher Medicare spending among people who disenrolled from Medicare Advantage for traditional Medicare raises several questions, including whether such switchers were unable to get the medical care they felt they needed while enrolled in a Medicare Advantage plan; whether more Medicare Advantage enrollees would make the switch if people with pre-existing conditions did not face barriers to purchasing Medicare supplemental insurance (Medigap); and whether the disenrollments reduce costs and increase profits for Medicare Advantage insurers, and increase Medicare spending. 

The analysis also drills down to examine differences in Medicare spending between switchers and those who were continuously covered by traditional Medicare by health condition, age, race and ethnicity, and dual eligible status.For the full analysis and other data and analyses about Medicare Advantage, visit kff.org.

Medicare Spending was 27% More for People who Disenrolled from Medicare Advantage than for Similar People in Traditional Medicare

Published: Dec 6, 2024

More than half (54%) of eligible Medicare beneficiaries are enrolled in a private Medicare Advantage plan in 2024. People are drawn to Medicare Advantage because most plans offer extra benefits and lower cost sharing compared to traditional Medicare without supplemental insurance, usually for no additional premium (other than the Part B premium). Medicare Advantage is also popular among lawmakers in Congress, both Republicans and Democrats, as well as President-elect Trump, whose previous administration generally supported policies that provided increased flexibilities to insurers when designing and administering these private plans.

Though Medicare Advantage is a popular choice for Medicare beneficiaries, there is some evidence that people who use relatively more health care services are less likely to choose a private plan and more likely to choose traditional Medicare. Previous analyses from KFF and the Medicare Payment Advisory Commission (MedPAC) found that people who enroll in Medicare Advantage have lower Medicare spending in the years before they enroll than similar people who remain in traditional Medicare, even after controlling for health status. This pattern may be partly attributable to concerns about the tools Medicare Advantage plans typically use to manage utilization and costs, such as prior authorization requirements and provider network restrictions.

This analysis looks at traditional Medicare spending among people who choose to disenroll from Medicare Advantage and obtain coverage under traditional Medicare during the annual Medicare open enrollment period. It compares their traditional Medicare spending (Parts A and B) in the year following disenrollment to similar people who were continuously covered by traditional Medicare (see Appendix for characteristics of each group), using data from the Medicare Master Beneficiary Summary File (MBSF) for 2021 and 2022 (see Methods).

Key Takeaways

  • Medicare spent 27% more, on average, for people who were covered by traditional Medicare after disenrolling from Medicare Advantage than for people who were continuously covered by traditional Medicare, after adjusting for differences in health status and other characteristics. This is a difference of $2,585 in Medicare spending per person, on average, between the two groups in 2022.
  • Differences in Medicare spending between people who disenrolled from Medicare Advantage and beneficiaries continuously in traditional Medicare varied by health condition, ranging from 15% for people with pneumonia to 34% for people with diabetes. For example, among people with certain cancers, Medicare spending was 28% ($4,907) higher, on average, among those who disenrolled from Medicare Advantage than among people continuously covered by traditional Medicare.
  • Differences in Medicare spending between people who disenrolled from Medicare Advantage and those continuously in traditional Medicare increased with age for Medicare beneficiaries ages 65 and over. For example, among people ages 85 and over the difference was 46% ($7,113) compared to 25% among people ages 65 to 69 ($1,843).
  • Differences in Medicare spending between people who disenrolled from Medicare Advantage and beneficiaries continuously in traditional Medicare were larger among Black (55%, $5,203) and Hispanic (54%, $4,434) beneficiaries than White beneficiaries (25%, $2,464).
  • People dually-eligible for Medicare and full Medicaid benefits who disenrolled from Medicare Advantage had spending that was 61% ($9,435) higher than their counterparts who were continuously in traditional Medicare, while the difference in spending for Medicare beneficiaries who do not receive Medicaid was 20% ($1,684).
  • Skilled nursing facility spending accounted for the largest share of the difference in average Medicare spending per person between people who disenrolled from Medicare Advantage and those continuously in traditional Medicare (34%), followed by outpatient hospital spending (23%), and inpatient hospital spending (20%), with some variation by chronic conditions and other beneficiary characteristics.

The substantially higher Medicare spending among people who disenrolled from Medicare Advantage, on average, compared to similar people who were continuously covered by traditional Medicare raises several questions. First, why are some Medicare Advantage enrollees choosing to disenroll from Medicare Advantage rather than get the medical care they need from their plan, and why are they receiving more medical care in the year following disenrollment than similar people who have been continuously covered by traditional Medicare?

Second, given how challenging it can be for people with pre-existing conditions to purchase Medicare supplemental insurance (Medigap) if they switch to traditional Medicare, and concerns about potentially high out-of-pocket costs under traditional Medicare without supplemental coverage, what share of Medicare Advantage enrollees would want to switch to traditional Medicare, but feel they cannot afford to do so?

Third, does the current payment system adequately account for adverse selection into traditional Medicare, which leads to higher Medicare Advantage benchmarks and higher payments to Medicare Advantage plans? Additionally, to what extent does the pattern of higher utilization and spending among people who disenroll from Medicare Advantage, reduce the costs incurred by insurers, increasing their profits and contributing to their ability to offer supplemental benefits? Finally, how does higher Medicare spending among people who disenroll from Medicare Advantage impact Medicare spending, and to what extent does it place added strain on the Medicare Hospital Insurance Trust Fund and increase beneficiary premiums?

People who disenrolled from Medicare Advantage had Medicare spending that was 27% more, on average, than spending for similar people continuously covered by traditional Medicare

Overall, people who disenrolled from Medicare Advantage had Medicare spending that was 27% ($2,585) higher, on average, than those continuously covered by traditional Medicare, after adjusting for differences in health risk factors (Figure 1).

Spending was $2,585 Higher (27%), on Average, Among People who Disenrolled from Medicare Advantage Compared to Those Continuously Covered by Traditional Medicare

Several studies have found that certain groups of Medicare Advantage enrollees switch to traditional Medicare at higher rates, including beneficiaries in their last year of life, those with higher health needs, and those dually eligible for Medicare and Medicaid. Furthermore, some groups with high disenrollment rates, such as beneficiaries in their last year of life, have higher health care spending after they disenroll compared to similar beneficiaries who are long-time recipients of traditional Medicare.

This analysis shows that spending differences are not limited to those particularly high-need groups because the spending differences persist after controlling for health risk, though the magnitude of the difference is greater, on average, for high-cost beneficiaries. While prior research finds lower health care spending among people who enroll in Medicare Advantage, in the year prior to enrollment, this analysis shows that people who disenroll from Medicare Advantage use more services and incur higher Medicare costs in the year following disenrollment than similar beneficiaries who were continuously covered under traditional Medicare.

People who disenrolled from Medicare Advantage had higher spending, on average, than those continuously covered by traditional Medicare across all chronic health conditions examined

People who disenrolled from Medicare Advantage had higher Medicare spending, on average, across all chronic health conditions examined, after adjusting for other health risk factors, than those continuously covered by traditional Medicare (Figure 2, Appendix Table 2). Differences in average per person spending varied by condition, ranging from 15% ($5,187) for people with pneumonia to 34% ($4,586) for people with diabetes. The largest difference in Medicare spending per person in dollar terms between people who disenrolled from Medicare Advantage and those continuously in traditional Medicare was among people with Alzheimer’s disease or other dementias ($7,451), followed by stroke ($6,660), and atrial fibrillation ($6,147). Among people with certain cancers, including breast, colorectal, endometrial, lung, prostate, and urologic cancers, spending for people who disenrolled from Medicare Advantage was 28% ($4,907) higher than for people continuously covered by traditional Medicare.

Spending Differences Between People who Disenrolled from Medicare Advantage and Those Continuously Covered by Traditional Medicare are Higher, on Average, Among Chronically Ill Beneficiaries Across All Chronic Conditions Examined

People with greater health needs may see multiple health care providers and require numerous specialty services, resulting in a greater burden from the limited provider networks, prior authorization, and referral requirements Medicare Advantage plans often employ. Prior authorization is most often required for high-cost services, such as chemotherapy and other Part B drugs, inpatient hospital stays, and stays in skilled nursing facilities. In addition, narrow provider networks may limit available options for treatment of certain conditions. For instance, prior studies have found that Medicare Advantage enrollees are less likely than traditional Medicare beneficiaries to receive care from the highest rated hospitals for treatment of cancer or cancer-related surgical procedures.

Average differences in Medicare spending between people who disenrolled from Medicare Advantage and those continuously covered by traditional Medicare increased with age among beneficiaries ages 65 and older

Across all age groups, people who disenrolled form Medicare Advantage had higher Medicare spending, on average, than those continuously covered by traditional Medicare. Average differences in per person spending increased with age among older beneficiaries, from 25% ($1,843) among those ages 65-69 to 46% ($7,113) among those ages 85 and older. People under the age of 65, who qualify for Medicare due to long-term disability, have somewhat higher average spending per person than Medicare beneficiaries between the ages of 65 and 74, and the differences in spending among this group between those who disenrolled from Medicare Advantage and those continuously covered by traditional Medicare were also somewhat larger (39%, $3,348) (Figure 3).

Spending Differences Between People who Disenrolled from Medicare Advantage and Those Continuously Covered by Traditional Medicare Increased with Age, on Average, Among Beneficiaries Ages 65 and Older

Average differences in Medicare spending between people who disenrolled from Medicare Advantage and those continuously covered by traditional Medicare were higher among Black and Hispanic than White beneficiaries

Across all racial and ethnic groups examined, people who disenrolled from Medicare Advantage had higher Medicare spending, on average, than those continuously covered by traditional Medicare. Average differences in per person spending were approximately two times higher among Black (55%, $5,203) and Hispanic (54%, $4,434) beneficiaries than among White beneficiaries (25%, $2,464) (Figure 4).

Spending Differences Between People who Disenrolled from Medicare Advantage and Those Continuously Covered by Traditional Medicare are Higher, on Average, Among Black and Hispanic Beneficiaries, Compared to White Beneficiaries

Average differences in Medicare spending between people who disenrolled from Medicare Advantage and those continuously covered by traditional Medicare were higher among people dually eligible for Medicare and full Medicaid benefits

Among dual-eligible beneficiaries who qualified for full Medicaid benefits, those who disenrolled from Medicare Advantage had spending that was 61% ($9,435) higher, on average, than those continuously covered by traditional Medicare. Average differences in per person spending were smaller among beneficiaries who were not dual-eligible (20%, $1,684) and among dual-eligible beneficiaries who qualified for assistance with Medicare premiums, and in some cases cost sharing, but not full Medicaid benefits (partial-benefit dual-eligible beneficiaries) (49%, $4,114) (Figure 5).

Spending Differences Between People who Disenrolled from Medicare Advantage and Those Continuously Covered by Traditional Medicare are Higher, on Average, Among People Dually Eligible for Medicare and Full Medicaid Benefits, Compared to Those with Partial or No Medicaid Benefits

Skilled nursing facility and hospital care accounted for more than three-quarters of the average difference in Medicare spending between people who disenrolled from Medicare Advantage and those continuously covered by traditional Medicare

Skilled nursing facility services accounted for the largest share (34%, $877) of the average difference in per person spending between people who disenrolled from Medicare Advantage and those continuously covered by traditional Medicare, followed by outpatient hospital services (23%, $596) and inpatient hospital services (20%, $505) (Figure 6).

Skilled Nursing Facility Care Accounted for One-Third of the Average Difference in Spending Between People who Disenrolled from Medicare Advantage and those Continuously Covered by Traditional Medicare

For certain groups, the total difference in average per person spending between people who disenrolled from Medicare Advantage and those continuously covered by Medicare Advantage was largely driven by skilled nursing facility services. These included dual-eligible beneficiaries with full Medicaid benefits (62%), beneficiaries ages 80 to 84 (59%) and ages 85 and older (55%), and beneficiaries with pneumonia (85%), Alzheimer’s disease or other dementias (74%), stroke (74%), and heart failure (73%) (Appendix Table 3). By contrast, skilled nursing facility services made up a smaller share of the total difference in average spending among people under age 65 (20%) and those ages 65 to 69 (14%).

Among other groups, inpatient hospital services made up a larger share of the difference in average spending, including among beneficiaries under age 65 with long-term disabilities (48%), as well as among beneficiaries with asthma (47%), glaucoma (33%), and chronic obstructive pulmonary disease (33%). Beneficiaries with certain cancers had among the highest share of the total difference in average spending attributed to outpatient hospital services (34%), a similar share attributed to skilled nursing facility services (30%) and a relatively modest share of the difference attributed to spending on inpatient hospital services (18%).

Consistent with this analysis, a recent report by the majority staff of the Senate Permanent Subcommittee on Investigations found that Medicare Advantage plans are more likely to deny prior authorization requests for coverage of post-acute care, such as skilled nursing facility stays, than for other types of services.

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

Selected Demographic Characteristics of Beneficiaries who Disenrolled from Medicare Advantage, Compared to Those Continuously Covered by Traditional Medicare
Average Spending Per Person Among Beneficiaries who Disenrolled from Medicare Advantage, Compared to Those Continuously Covered by Traditional Medicare
Average Difference in Spending Per Person by Service Category Among Beneficiaries who Disenrolled from Medicare Advantage, Compared to Those Continuously Covered by Traditional Medicare

This analysis uses data from the 20% Medicare Master Beneficiary Summary File (MBSF) and Medicare claims files to compare Medicare spending (across Parts A and B) for beneficiaries who were previously enrolled in Medicare Advantage (Disenrolled from Medicare Advantage) to beneficiaries who have been continuously covered by traditional Medicare (Always Traditional Medicare). The Disenrolled from Medicare Advantage cohort includes people who were enrolled in Medicare Advantage in 2021 and in traditional Medicare in 2022. The Always Traditional Medicare cohort of beneficiaries were enrolled in traditional Medicare in both 2021 and 2022.

To be included in either cohort, beneficiaries had to have 12 months of coverage under Medicare Part A and Part B in 2021, as well as coverage in Parts A and B in all months in 2022 they were enrolled in Medicare (i.e., not deceased). The analysis includes all 50 states and DC. People with ESRD are excluded because 2021 was the first year people with ESRD were broadly eligible to enroll in a Medicare Advantage plan. For the Disenrolled from Medicare Advantage cohort, the analysis excludes people who were enrolled in a cost plan, Medicare Medicaid plan, or PACE plan in 2021.

Compared to the Always Traditional Medicare cohort, a somewhat larger share of the Disenrolled from Medicare Advantage cohort were ages 65 to 69 (24% vs. 17%), Black (10% vs. 7%) or Hispanic (7% vs. 5%), or dually eligible for Medicare and full Medicaid benefits (16% vs. 12%). There were also differences in the share of beneficiaries with certain health conditions (Appendix Table 1). To account for differences in age, dual eligibility, and health status, the risk score for each person was calculated using the CMS-HCC Risk Adjustment model based on diagnoses present in 2022. Note that the risk model is used to adjust payments to Medicare Advantage plans and does not account for race. Thus our approach also does not control for race and ethnicity.

Compared to all people enrolled in Medicare Advantage in 2021, those who disenrolled were more likely to have been covered by traditional Medicare in 2020 than those who stayed enrolled in Medicare Advantage. Specifically, among people who disenrolled from Medicare Advantage, 31% were covered by traditional Medicare in 2020; among people who stayed in Medicare Advantage, 11% were in traditional Medicare in 2020. These differences may be driven by the ability for people to return to the same Medigap policy within 12-months after switching to Medicare Advantage for the first time (note, Medicare beneficiaries are limited to a single “trial period”), relieving concerns about Medigap underwriting or cost sharing without a supplemental policy for some subset of people who disenrolled. We are unable to determine what share of the people who disenrolled from Medicare Advantage were in their “trial period” because it was the first time they had tried Medicare Advantage.

Our approach to analyzing spending follows the approach used by MedPAC in calculating average spending for people who switch from traditional Medicare to Medicare Advantage compared to those who remain in traditional Medicare. First, all Medicare payments, beneficiary liability, and other primary payer payments for all Part A and Part B services were summed for each person in the sample for Calendar Year 2022. Next, each person’s total spending is divided by their risk score (calculated using the CMS-HCC Risk Adjustment model and 2022 diagnoses) to derive risk-standardized spending, which allows for comparisons on an apple-to-apple basis for people with differences in health risk (such as differences in diagnosed health conditions). Within each county, the risk-standardized spending for each cohort is then averaged. To estimate spending given the health risk of the population of people who disenrolled from Medicare Advantage, the risk-standardized spending is then multiplied by the average risk score of people who disenrolled from Medicare Advantage. The national average spending for each cohort is then calculated as a weighted average of each county spending, using the number of people who disenrolled from Medicare Advantage as the weight. Counties in which no beneficiaries disenrolled from Medicare Advantage are excluded from the analysis. For each subgroup analysis a similar approach is followed, limiting the sample to people with the specific characteristic.

The Medicare Chronic Conditions Warehouse definitions for chronic conditions were used as a basis for identifying people with specific chronic conditions. To maintain consistency across the cohorts, only the 2022 claims were used. At least 1,000 members of the Disenrolled from Medicare Advantage cohort had to have a chronic condition for it to be included in the list.

Additionally, to test the sensitivity of the analysis, spending was modeled using a regression that controlled for risk score and county. The regression was specified using both a general linear model with a log link and a probit model. The average difference in each case was similar to those presented in this brief.

Overview of Medicare Advantage Payments

Medicare pays Medicare Advantage plans, in part, based on county-level spending for similar people in traditional Medicare, though payments may be higher or lower depending on a range of factors, such as a plan’s quality star rating, the county in which it operates, and the amount requested annually by the plan (referred to as a plan’s “bid”).

Plans that bid above traditional Medicare spending must charge enrollees an additional premium to make up the difference in cost. A growing number of plans choose to bid below traditional Medicare spending, which allows them to recoup a portion of the savings as a “rebate.” Rebates must be put towards certain plan features, such as lower cost-sharing, reductions to enrollees’ Part B or Part D premiums, or extra benefits (such as dental, vision, and hearing) not included in traditional Medicare. Payments are further adjusted to reflect the health status of enrollees, as well as certain other characteristics, such as age, sex, and Medicaid enrollment. Plans whose enrollees are expected to incur larger health costs receive larger payments (a process referred to as “risk adjustment”).

The Medicare Payment Advisory Commission estimates that payment to Medicare Advantage insurers is 122% of Medicare spending for similar beneficiaries covered by traditional Medicare. The higher payments are driven by favorable selection into Medicare Advantage and more intense coding of diagnoses among these plans. Those higher payments allow Medicare Advantage insurers to offer additional benefits and lower out-of-pocket spending, but place pressure on the hospital insurance trust fund and raise Medicare Part B premiums for all beneficiaries, including those in traditional Medicare.

With or Without ACA Repeal, ACA and Medicaid Cuts are Looming

Author: Larry Levitt
Published: Dec 5, 2024

In this JAMA Health Forum column, KFF Executive Vice President Larry Levitt explores why the incoming Trump administration and Republican majorities in Congress are likely to pursue budget cuts in Medicaid and the Affordable Care Act and why such efforts are likely to boost the number of uninsured Americans while shifting financial responsibility and decision-making to the states.

The U.S. & The Global Fund to Fight AIDS, Tuberculosis and Malaria

Published: Dec 3, 2024

This fact sheet does not reflect recent changes that have been implemented by the Trump administration, including a foreign aid review and restructuring. For more information, see KFF’s Overview of President Trump’s Executive Actions on Global Health.

Key Facts

  • The Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund), founded in 2002, is an independent, multilateral financing entity designed to raise significant resources and accelerate efforts to end the HIV, tuberculosis (TB), and malaria epidemics.
  • The U.S. government (U.S.), which provided the Global Fund with its founding contribution, is its largest single donor; between FY 2001 and FY 2024 regular Congressional appropriations to the Global Fund totaled approximately $26 billion. In FY 2021, an additional $3.5 billion was provided by Congress as emergency funding to respond to the COVID-19 pandemic.
  • The U.S. also plays a key role in the organization’s governance and oversight, having its own Board seat and sitting on two of the Board’s committees.
  • As of October 2024, the Global Fund had approved more than $78 billion in funding to almost 130 countries for its core HIV, TB, and malaria programs; the Global Fund estimates these investments have helped to save 65 million lives. In addition to its core programmatic activities, the Global Fund played a major role in COVID-19 response efforts, awarding over $5 billion to respond to COVID-19 as of July 2024, and continues to support countries as they shift from emergency pandemic response to longer-term health systems strengthening and pandemic preparedness efforts.
  • The Global Fund’s eighth replenishment cycle, where it will mobilize resources from donors for its next funding cycle, will take place in 2025.

What is the Global Fund?

Overview

The Global Fund is an independent, multilateral financing entity designed to raise significant new resources to combat HIV, tuberculosis (TB), and malaria in low- and middle- income countries. First proposed in 2001, the Global Fund began operations in January 2002 and receives funding from both public and private donors to finance programs developed and implemented by recipient countries. The Global Fund uses a “country-defined” and “results-based financing” model that focuses on country ownership and is supported by investments from both donors and implementing countries (by contrast, bilateral support is provided from donors directly to recipient country governments, non-governmental organizations, and other entities and often reflects donor-defined priorities). To date, approximately $89 billion1  has been pledged by all donors (governments, the private sector, and private foundations) to the Global Fund, including $15.7 billion at the latest replenishment conference for the 2023-2025 funding cycle. Using these resources, the Global Fund has approved more than $78 billion in grants to almost 130 countries2  for its core HIV, TB, and malaria programs, and awarded over $5 billion in funding to respond to the COVID-19 pandemic’s impact on efforts related to these three epidemics.3  The Global Fund’s eighth replenishment cycle, where it will mobilize resources from donors for its next funding cycle, will take place in 2025.

The U.S. has played an integral role in the Global Fund since its inception. Under the George W. Bush administration, the U.S. provided the Global Fund with its founding contribution and was involved in the initial negotiations on the multilateral organization’s design. Under the Obama administration, the U.S. pledged $12.3 billion to the Global Fund over three replenishment periods.4  The Trump administration had proposed funding cuts to the Global Fund and a reduced pledge amount, although Congress rejected these proposals.5  The Biden administration signaled increased support for the Global Fund, particularly given its direct role in responding to the COVID-19 pandemic (see the Global Fund & COVID-19 section below), and pledged $6 billion over a three-year period6  at the latest replenishment conference in September 2022. The U.S. also provided an additional $3.5 billion in FY 2021 emergency funding to the Global Fund to address the impact of COVID-19 on HIV, TB, and malaria programs.

In addition to being the Global Fund’s single largest donor (see Table 1), the U.S. has a permanent seat on the Board of the Global Fund, giving it a key role in governance and oversight.7  The Global Fund has been called the “multilateral component” of the U.S. President’s Emergency Plan for AIDS Relief (PEPFAR), the U.S. government’s global effort to combat HIV (see the KFF fact sheet on PEPFAR), serving as a significant part of the U.S. government’s global health response, expanding its reach to more countries, and leveraging additional donor resources.

Still, long-ongoing discussions include the appropriate balance of U.S. funding between the Global Fund and U.S. bilateral programs, how to ensure the Global Fund’s sustainability and ability to provide the needed level of support (particularly given continued high demand for its support from countries, even amid a shortfall in available resources), and more broadly, the role of multilateralism in U.S. global health policy.8  Further, the appropriate shape of its role in strengthening health and community systems and, more broadly, pandemic preparedness and response, (its latest strategy includes a new pandemic preparedness and response objective) is also the subject of discussion.9 

Global Fund Pledges and Contributions, as of October 2024 (Table)

Funding Model & Organizational Structure10 

The Global Fund was established as an independent foundation under Swiss law and operates as a multilateral financing entity. Funding is pooled from multiple sources, including from donor governments, the private sector, and private foundations. Countries submit proposals to the Global Fund, and if approved, funding is provided using a performance-based system where a grant is regularly monitored and evaluated to determine if it should be extended or discontinued based on the effectiveness of the program. Eligibility for funding is based on a country’s income classification and disease burden.11  Also, in order to incentivize recipient countries to increase their domestic investments and increase country ownership (ultimately preparing countries for graduation from Global Fund support), the Global Fund includes a policy that at least 15% of funding is conditional upon increases in co-financing (see KFF brief on co-financing for more).12 

The Global Fund’s organizational structure includes a broad set of stakeholders, and the U.S. government is involved in many of its core structures:

  • Board. The Board guides policy and strategic decisions and approves all funding. There are 20 voting members (10 implementers and 10 donors) and 8 non-voting members as follows:
    • Implementers:
      • Developing countries: seven members, one from each of the six WHO regions and an additional member from Africa.
      • Civil Society: three members, one from a developing country non-governmental organization (NGO), one from a developed country NGO, and one representative from an NGO who is a person living with HIV/AIDS or from a community living with TB or malaria.
    • Donors:
      • Government: eight members, including the U.S., which has a permanent Board seat. The U.S. also sits on the Audit & Finance and Ethics & Governance Committees.
      • Private Sector: one member.
      • Private Foundation: one member.
    • Non-voting: eight members, including the Global Fund Executive Director, the Board Chair and Vice-Chair, one representative from Global Fund partner organizations, one representative each from WHO, UNAIDS, and the World Bank, and one representative from certain public donors that are not part of a voting donor constituency.
  • Secretariat. Based in Geneva, the Secretariat manages day-to-day operations. Because the Global Fund finances but does not implement programs, it does not maintain any in-country staff.
  • Office of the Inspector General. An independent body of the Global Fund that reports directly to the Board through its Audit and Finance Committee, the Office of the Inspector General provides the Board with audits and investigations of the Fund’s activities, in an effort to promote good practices, reduce funding risks, and report on potential abuse.
  • Technical Review Panel (TRP). An independent body of global health and development experts (which has included U.S. government experts) appointed by the Board to evaluate the merits of all proposals and make funding recommendations to the Board.
  • Independent Evaluation & Learning. An independent body consisting of an Evaluation & Learning Office and Independent Evaluation Panel (IEP) that provides advisory services and oversight on the Fund’s evaluation efforts, including progress toward achieving the goals laid out in its strategy.13 
  • Country Coordinating Mechanisms (CCMs). The country-level entity comprised of public and private sector representatives, such as governments, businesses, and NGOs, that submits proposals to the Global Fund and oversees funded grants within a country. U.S. representatives sit on CCMs in almost all PEPFAR focus countries and often help with proposal development. The U.S. has also entered into a memorandum of understanding (MOU) in several countries to bring together PEPFAR with Ministries of Health and the Global Fund to clarify collaboration and partnership activities, particularly in the area of antiretroviral drug procurement.
  • Principal Recipients (PR). The legal entity chosen by the CCM to receive Global Fund disbursements, implement programs or contract with sub-recipients, and provide regular reports and progress updates to the Secretariat.
  • Local Funding Agents (LFA). Since it does not have an in-country presence, the Global Fund contracts with a local entity (usually an accounting firm) to monitor program implementation, ensure financial accountability, and provide funding recommendations to the Secretariat.

Results

The Global Fund, which was the second largest donor to global health programs in 2022 (the U.S. was the largest),14  estimates that, since 2002, its grants have helped save the lives of 65 million people who would have otherwise died due to complications from AIDS, TB, or malaria and reduced the combined death rate from these three diseases by 61%. As of October 2024, the Global Fund had approved more than $78 billion in funding for its core HIV, TB, and malaria activities and, as of July 2024, awarded over $5 billion in funding to respond to COVID-19 (see the Global Fund & COVID-19 section below).15  Funding supports a wide range of prevention, treatment, and care activities and health systems development and strengthening. Most approved funding has supported HIV programs, followed by malaria and TB (see Table 2). This funding has reached almost 130 countries,16  including not only countries that also have received U.S. bilateral support for HIV, TB, and/or malaria but also many others that have not.17  The African region has received the largest share of approved funding (68%), followed by South-East Asia (11%).18 

Global Fund Portfolio Status, as of October 2024 (Table)

U.S. Engagement with the Global Fund

In addition to U.S. engagement in governance and oversight of the Global Fund, U.S. financial support has been significant and is a key component of U.S. involvement (see figure).19  The U.S. first contributed to the Global Fund in FY 2001, and then upon the creation of PEPFAR in 2003, Congress incorporated all U.S. support for the Global Fund under the PEPFAR umbrella. At that time, Congress authorized up to $1 billion for the Global Fund for FY 2004 and “such sums as may be necessary” for FY 2005-FY 2008. In the 2008 reauthorization of PEPFAR, Congress authorized up to $2 billion in FY 2009 and “such sums as may be necessary” for FY 2010-FY 2013.” In 2013, 2018, and 2024, Congress again reauthorized PEPFAR, and while those reauthorizations included provisions related to U.S. support for the Global Fund (see below), they did not include specific funding authorization amounts. Since the 2024 reauthorization was a short-term extension (through March 2025), discussions about the next reauthorization of PEPFAR, including expiring provisions related to the Global Fund, are ongoing. See the KFF policy watch on PEPFAR reauthorization key issues as well as the KFF brief on PEPFAR legislation over time.

U.S. Funding for The Global Fund, FY 2016 - FY 2025

Congress specifies support for the Global Fund each year as part of PEPFAR appropriations, and funding is typically provided through the Department of State, although funding has also been provided through USAID and NIH in past years. Between FY 2001 and FY 2024, regular Congressional appropriations to the Global Fund totaled approximately $26 billion.20  In FY 2021, an additional $3.5 billion was provided as emergency funding to respond to the COVID-19 pandemic.21  Congress has historically matched or provided more to the Global Fund each year than the President has requested. (See the KFF budget tracker and the KFF fact sheet on the U.S. Global Health Budget: Global Fund for details on historical appropriations for the Global Fund.)

While Congress has provided strong funding support for the Global Fund, it has also regularly passed provisions that placed restrictions on U.S. contributions:22 

  • Requiring that total U.S. contributions do not exceed 33% of total contributions from all donors, a provision that was part of the original PEPFAR authorization and maintained in the reauthorizations. Designed to leverage U.S. contributions to increase support from other donors and to limit the U.S. from becoming the predominant donor to the Global Fund, it was invoked only once, in FY 2004 when appropriated funds were held back until the following fiscal year when the 33% cap would not be exceeded.
  • Setting aside 5% of U.S. contributions to cover the cost of technical assistance to Global Fund grantees, a provision first included in foreign operations appropriations bill language in 2005 and in subsequent years.
  • Authorizing the Secretary of State to withhold a percentage of the U.S. contribution until the Global Fund could demonstrate improved oversight and accountability in grant disbursement.
  • Requiring, as part of the FY 2012 through FY 2024 appropriations bills, that the administration consult with Congress prior to making multi-year funding pledges.

The Global Fund & Emergency Responses

COVID-19

Since the beginning of the COVID-19 pandemic, the Global Fund acted to support countries in their efforts to address COVID-19’s impact on HIV, TB, and malaria programs. The Global Fund established a “COVID-19 Response Mechanism” (C19RM) in April 2020, and also allowed for grant flexibilities that gave countries the ability to use a certain percentage of their current grants for COVID-19 response activities. As of July 2024, the Global Fund had awarded over $5 billion in funding to more than 100 countries to support countries’ responses to COVID-19.23  Support from the Global Fund to countries was used to:

  1. support national COVID-19 response efforts, including purchasing tests, treatments, and medical supplies;
  2. mitigate COVID-19’s impact on Global Fund-supported programs; and
  3. improve health and community-led response systems.

As countries shifted from emergency pandemic response to longer-term efforts, the Global Fund allowed countries to reprogram their C19RM funds for health systems strengthening and pandemic preparedness activities. Today, the Global Fund reports that its partner countries have made a full recovery from the impacts of the COVID-19 pandemic and that service delivery metrics have surpassed pre-COVID-19 levels.

Mpox

Since Mpox was first declared a public health emergency of international concern in 2022, the Global Fund has worked to strengthen partner countries’ response to Mpox outbreaks by allowing grant flexibilities and repurposing of funds from HIV grants and C19RM funding. Specifically, countries may request support from Global Fund grants for activities such as disease surveillance, laboratory system strengthening, strengthening the workforce, as well as community engagement.

  1. Includes pledges through 2025. Includes COVID-specific emergency contributions. ↩︎
  2. Does not include countries that may have received funding through multi-country or regional programs. Additional countries may be reached through multi-country or regional programs. ↩︎
  3. Core activities represent HIV, TB, HIV/TB, malaria, multi-purpose, and Resilient & Sustainable Systems for Health (RSSH) funding only; the more than $78 million in approved funding does not include a breakdown of COVID-specific amounts as they cannot be attributed to a specific area, such as HIV, TB, or malaria. KFF analysis of The Global Fund Data Service: https://data-service.theglobalfund.org/downloads; accessed October 2024. The Global Fund, Dataset: Funding Approved for COVID-19 Response; July 2024. ↩︎
  4. The U.S. pledged $4 billion in both the FY11-FY13 and FY14-16 replenishment cycles and $4.3 billion in the FY17-FY19 replenishment cycle. U.S. State Department, Obama Administration’s Pledge to Global Fund to Fight HIV/AIDS, Malaria and Tuberculosis, October 5, 2010. The Global Fund, Fourth Voluntary Global Fund Replenishment Pledges, December 2013. White House, Office of the Press Secretary. Statement by National Security Advisor Susan E. Rice on the United States' Global Fund Pledge; August 31, 2016. ↩︎
  5. Fulfillment of a pledge is dependent on annual Congressional appropriations. The Trump administration proposed reducing U.S. contributions to the Global Fund in each of its annual budget requests to Congress. In addition, the Trump administration proposed a pledge of $3.3 billion, matching $1 for every $3 contributed by other donors for the next replenishment period, a decline of more than $1.0 billion compared to the U.S. pledge during the prior replenishment period under the Obama administration (up to $4.3 billion, matching $1 for every $2 provided by other donors). See U.S. Department of State, FY2021 Congressional Budget Justification – Department of State, Foreign Operations, and Related Programs, February 2020. ↩︎
  6. The pledge period for the Global Fund’s seventh replenishment is 2023-2025. ↩︎
  7. Global Fund: http://www.theglobalfund.org/; as of September 2024. KFF analysis. White House, President Announces Proposal for Global Fund to Fight HIV/AIDS, Malaria and Tuberculosis; May 11, 2001. ↩︎
  8. Global Fund, The Global Fund Strategy 2023-2028, November 2021. The Global Fund, Thematic Report: Pandemic Preparedness and Response, May 2022. ↩︎
  9. Global Fund, Results Report 2024, September 2024. ↩︎
  10. Center for Global Development, Overview of the Global Fund to Fight AIDS, Tuberculosis and Malaria. ↩︎
  11. All low- and lower-middle-income countries are eligible for Global Fund grants regardless of disease burden; disease burden criteria only apply to upper-middle-income countries to determine their eligibility. ↩︎
  12. The Global Fund funding model includes a co-financing requirement for countries to show progressive government spending on health and progressive up-take of recurrent costs associated with key programs, as well as a co-financing incentive that at least 15% of a country’s allocation is withheld until the country has committed to additional investments over and above previous levels of spending. Global Fund, Website: Funding Model: Throughout the Cycle: Co-financing, available at: https://www.theglobalfund.org/en/funding-model/throughout-the-cycle/co-financing/. ↩︎
  13. The Independent Evaluation & Learning function replaces the Technical Evaluation Reference Group (TERG). Global Fund, Website: Independent Evaluation & Learning, available at: https://www.theglobalfund.org/en/iel/; accessed September 2024. ↩︎
  14. KFF analysis of OECD DAC CRS database, June 2024. ↩︎
  15. KFF analysis of the Global Fund Data Explorer: https://data.theglobalfund.org/home; accessed September 2024. The Global Fund, Dataset: Funding Approved for the COVID-19 Response; July 2024. ↩︎
  16. Does not include countries that may have received funding through multi-country or regional programs. Additional countries may be reached through multi-country or regional programs. ↩︎
  17. KFF analysis of the Global Fund Data Explorer: https://data.theglobalfund.org/home; accessed October 2024. ↩︎
  18.  KFF analysis of the Global Fund Data Explorer: https://data.theglobalfund.org/home; accessed October 2024. Regions based on WHO regional classifications. ↩︎
  19. KFF analysis of data from the Office of Management and Budget, Agency Congressional Budget Justifications, Congressional Appropriations Bills, and U.S. Foreign Assistance Dashboard [website], available at: www.foreignassistance.gov. ↩︎
  20. This amount ($26 billion) represents the total amount of funding specified by Congress through FY 2024. However, the $32 billion pledged by the U.S. (seen in Table 1) includes the latest replenishment which runs through 2025, so the amounts will not match. ↩︎
  21. KFF analysis. The American Rescue Plan Act of 2021 included $3.75 billion “to support programs for the prevention, treatment, and control of HIV/AIDS in order to prevent, prepare for, and respond to coronavirus, including to mitigate the impact on such programs from coronavirus and support recovery from the impacts of the coronavirus,” of which not less than $3.5 billion was for the Global Fund. U.S. Congress, Public Law No: 117-2; March 11, 2021. KFF, Global Funding Across U.S. COVID-19 Supplemental Funding Bills, March 2021. ↩︎
  22. KFF analysis. U.S. Congress, Public Law No: 110-293; July 30, 2008. U.S. Senate Committee on Foreign Relations (Minority Staff Report), Fraud and Abuse of Global Fund Investments at Risk without Greater Transparency; April 5, 2011. U.S. Congress, Public Law No: 112-74; December 23, 2011. KFF, PEPFAR Reauthorization: Side-by-Side of Legislation Over Time, August 18, 2022. ↩︎
  23. Global Fund, Dataset: Funding Approved for COVID-19 Response; July 2024. ↩︎