Medicare Cuts to 340B Drug Payments Will Hit Safety-Net Hospitals While Benefiting For-Profit Hospitals
Editorial Note: Originally published on July 29, 2026, this brief has been updated to reflect changes in the final rule.
The recently finalized 2027 Medicare Hospital Outpatient Perspective Payment System (OPPS) rule from the Centers for Medicare & Medicaid Services (CMS) includes a rule to reduce Medicare’s reimbursement for 340B drugs. The rule will reduce reimbursement for 340B drugs from average sales price (ASP) plus 6% (what Medicare generally pays for Part B outpatient drugs administered by providers) to ASP minus 28%, a 32% reduction (CMS originally proposed reducing reimbursement to ASP minus 33.4%). CMS indicated that this change will better align Medicare reimbursement with hospitals’ costs of acquiring 340B drugs.
The 340B Drug Pricing Program requires drug manufacturers participating in Medicaid to sell outpatient drugs to eligible nonprofit and government providers at a substantial discount, allowing providers to earn larger profits when being reimbursed for 340B drugs. The intent of the program is to support providers, such as certain disproportionate share hospitals and federally qualified health clinics, that care for low-income and other underserved populations. Critics have raised concerns that the 340B program, which has grown substantially over time, is not well-targeted; that savings from the program are not shared with patients; and that the program incentivizes hospitals to acquire clinics and physician practices in order to extend 340B discounts to those settings, enabling them to generate more revenue. Supporters of the program say that revenues generated by the difference between Medicare (and other payer) reimbursement for 340B drugs and the discounted price help 340B providers care for underserved populations and invest in operations.
CMS based the amount of the payment reduction on the maximum allowed acquisition costs under the 340B program, after also considering a cost acquisition survey of 340B drugs completed by hospitals in early 2026 (CMS originally proposed setting reimbursement to ASP minus 33.4% based on the survey, but set reimbursement using the maximum allowed acquisition costs in the final rule to simplify future updates, among other reasons). This change revives an earlier effort by CMS to reduce Medicare payments for 340B drugs that was implemented in 2018 under the first Trump administration, but the Supreme Court overturned that rule in 2022 because the agency had not first conducted a cost acquisition survey. CMS’s Medicare 340B payment reduction will take effect on January 1, 2027, and will have disparate effects on different types of hospitals, as described more below.
CMS’s finalized cut to 340B drug reimbursement will reduce Medicare spending on 340B drugs by an estimated $4.65 billion in 2027, while increasing spending on non-drug outpatient services by the same amount because of budget neutrality requirements. Under federal law, CMS is generally required to maintain the same amount of aggregate spending through OPPS regardless of reimbursement changes (i.e., maintain budget neutrality). Based on this requirement, CMS finalized a 7.5% across-the-board increase in payments for non-drug outpatient services covered under the OPPS, which the agency estimates will offset the impact of cuts to spending on 340B drugs in 2027.
The budget neutrality requirement means that savings from reductions in 340B payments to 340B hospitals would be redistributed to both 340B and non-340B hospitals through higher payments for non-drug outpatient services. Similarly, Medicare beneficiaries would face lower cost sharing on 340B drugs (e.g., based on 20% coinsurance applied to a lower amount) but higher cost sharing for non-drug outpatient hospital services. CMS estimates that Medicare beneficiaries who use 340B drugs would save $1.1 billion in total in 2027, but cost sharing would increase for beneficiaries who use non-drug outpatient hospital services based on Medicare’s proposed 7.5% payment increase.
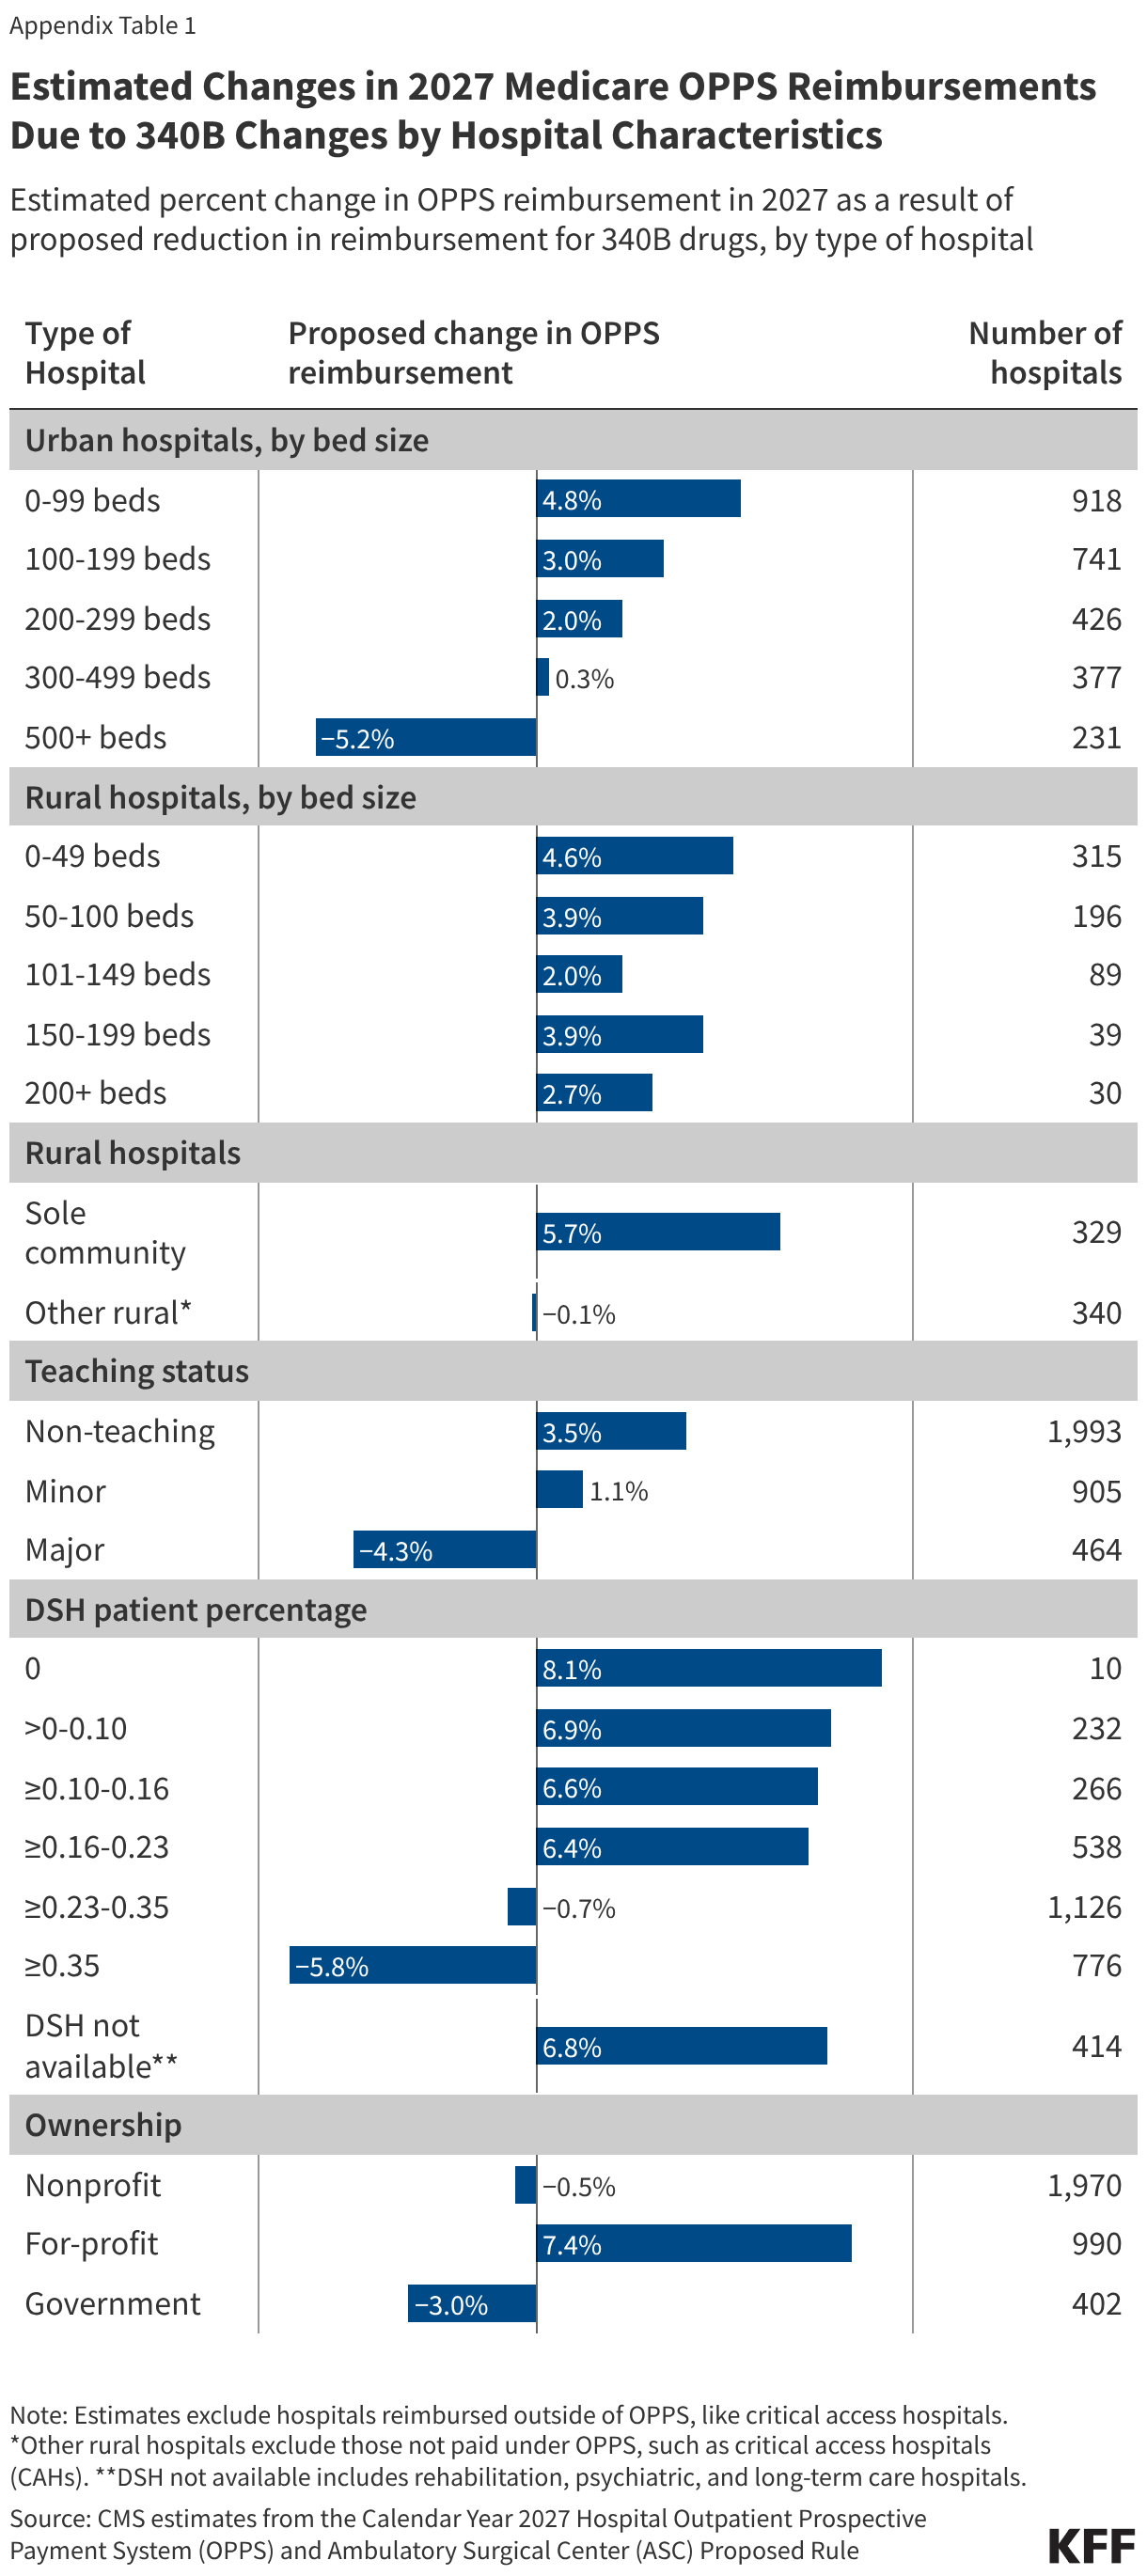
Proposed cuts will reduce revenues among safety-net hospitals while increasing revenues among for-profit hospitals, among other differences. For 340B hospitals, total Medicare revenues will decrease or increase depending on how reliant they are on revenues from 340B drugs versus non-drug outpatient services, but non-340B hospitals would experience revenue increases only based on the higher payment rate for non-drug outpatient services. CMS’s rule to reduce reimbursement for 340B drugs will exempt rural sole community hospitals (SCHs) (rural hospitals that are the only source of short-term, acute inpatient care in a region), children’s hospitals, and PPS-exempt cancer hospitals. Changes will not affect hospitals that are not reimbursed under the OPPS, including critical access hospitals (CAHs), which make up the majority of rural hospitals.
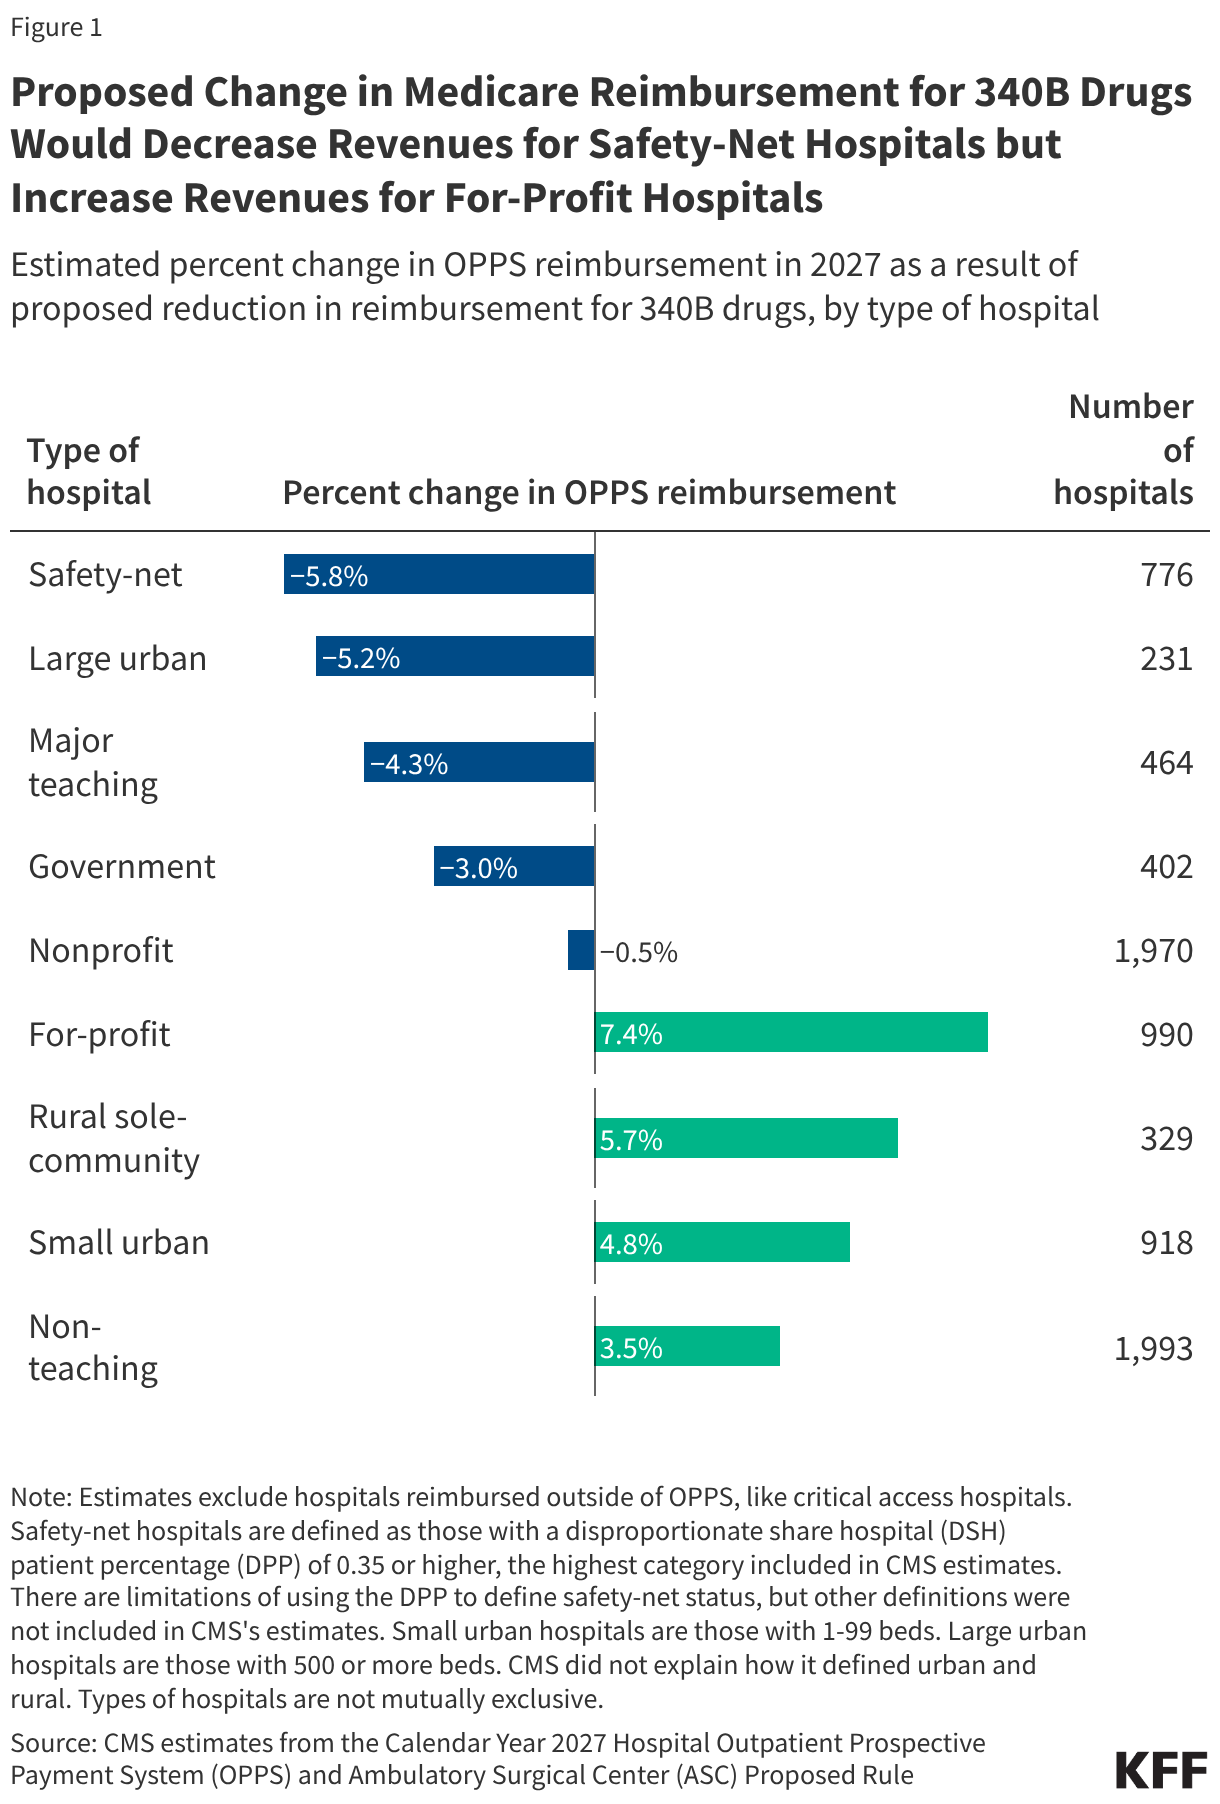
In the aggregate, some types of hospitals will lose or benefit more from these changes than others, based on estimates from CMS (Figure 1):
- Safety-net hospitals will face a 5.2% net reduction of OPPS revenue under this proposal (see figure notes for definition of “safety-net hospitals”). Other types of hospitals will also see net reductions in OPPS revenue in the aggregate, including large urban hospitals (with 500 beds or more) (-4.8%), major teaching hospitals (-3.9%), government hospitals (-2.9%), and nonprofit hospitals (-0.4%). Some hospitals that will see the largest decrease in revenue likely fall into more than one of these categories (e.g., major teaching hospitals tend to be large urban hospitals).
- For-profit hospitals will see a 6.8% net increase in OPPS revenues. For-profit hospitals are not eligible for the 340B program and so will only see increases in reimbursement for non-drug outpatient services. Other types of hospitals will also face net increases in Medicare OPPS reimbursement in aggregate, including rural SCHs (5.3%), small urban hospitals (with 0 to 99 beds) (4.5%), and non-teaching hospitals (3.5%).
Reductions in 340B payments could add to the financial challenges facing safety-net hospitals while increasing margins of for-profit hospitals. Safety-net hospitals have lower operating margins than average and so could have an especially difficult time absorbing any revenue losses from the 340B payment cut, while for-profit hospitals have much higher operating margins than the average hospital. Additionally, safety-net hospitals, which are particularly dependent on Medicaid revenues, are likely to be disproportionately affected by the 2025 reconciliation law, as it achieves most of its health care savings through federal Medicaid spending reductions.
The substantial growth of the 340B program in recent years has led hospitals, pharmaceutical companies, and policymakers to focus on whether and how to change the program. At the federal level, lawmakers have proposed options that would preserve or narrow the scope of the program and have proposed increasing transparency around the program, such as by requiring hospitals to report 340B savings. At the state level, some states have passed laws that would preserve the ability of hospitals to use multiple contract pharmacies to dispense 340B drugs, among other things. Other states have implemented requirements for hospitals to disclose the amount of savings generated from the 340B program (as required by Minnesota) or how those savings are spent.
Some pharmaceutical companies have attempted to start providing 340B drug discounts through a rebate model, an approach that would require hospitals to purchase 340B drugs at a non-discounted price and receive post-sale rebates after submitting claims information. These efforts have been halted by the courts due to lack of authorization from HHS, the agency that administers the 340B program. In 2025, the Trump administration attempted to implement the 340B Rebate Model Pilot Program, but a court halted the pilot after a lawsuit was filed by the hospital industry. HHS announced a revised rebate model pilot in July 2026, which has also been challenged in court.
Appendix