Medicare Advantage in 2026: Enrollment Update and Key Trends

Published: Jun 5, 2026

Editorial Note


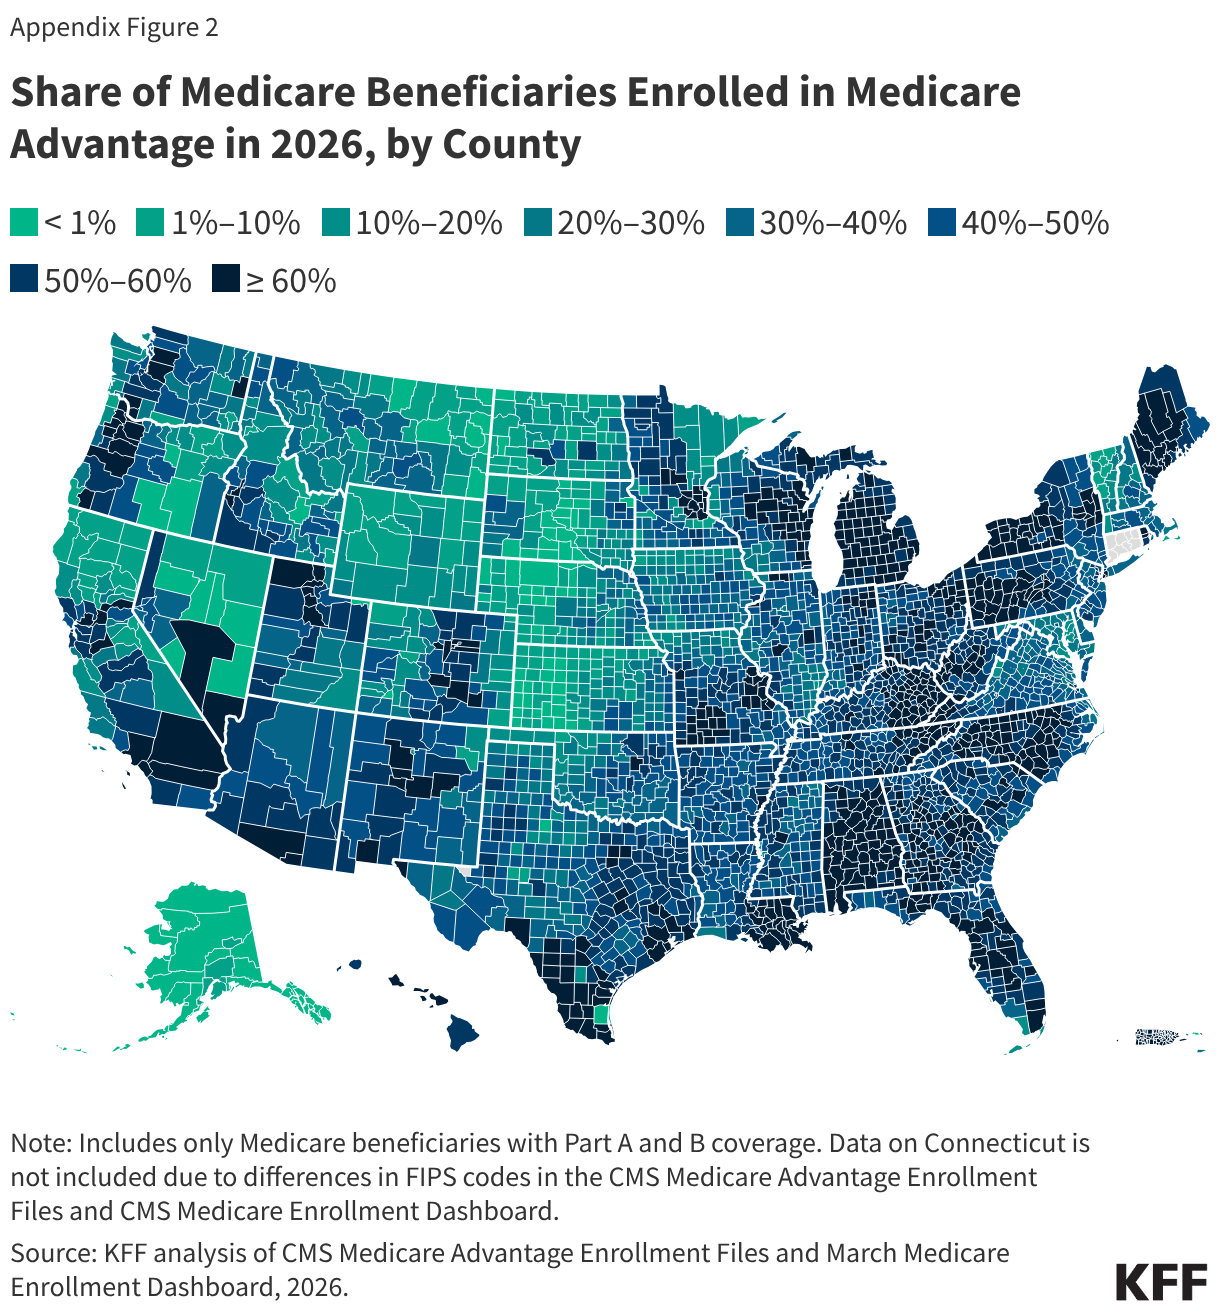
This analysis has been updated July 1, 2026 to reflect March 2026 data for overall Medicare Advantage penetration, though the Medicare Advantage penetration rate remains at 55%. It also now includes Medicare Advantage penetration by state and county (see Appendix figures).

Enrollment in Medicare Advantage, the private plan alternative to traditional Medicare, has increased steadily over the past two decades, with more than half of eligible beneficiaries enrolled in Medicare Advantage since 2023. The growth in enrollment has implications for federal spending, because according to the Medicare Payment Advisory Commission (MedPAC), Medicare payments to private plans are higher than spending for similar beneficiaries in traditional Medicare. In 2026, payments are 14% more per person, which translates into an additional $76 billion in federal spending this year. While payments per person relative to traditional Medicare are similar to a decade ago (15% higher), the impact on federal spending was substantially lower at $24 billion because enrollment was substantially lower with about one-third of eligible beneficiaries enrolled in a Medicare Advantage plan at that time.

Given the enrollment and spending trends, policymakers have become increasingly focused on how Medicare pays private plans, though without broad agreement on how or when to move forward with any changes to how Medicare Advantage plans are paid. In part, the difficulty stems from concerns about the effects of payment changes on beneficiaries’ choice among plans and access to supplemental benefits, such as coverage of dental, vision and hearing.

To better understand trends in the growth of the Medicare Advantage program, this brief provides current information about enrollment, including by plan type and firm. A second, companion analysis describes Medicare Advantage premiums, out-of-pocket limits, supplemental benefits offered, and prior authorization requirements in 2026.

Highlights for 2026:

  • More than half (55%) of eligible Medicare beneficiaries are enrolled in Medicare Advantage in 2026. While a growing share of Medicare beneficiaries are enrolled in a Medicare Advantage plan, the pace of the increase in enrollment continued to slow in 2026.
  • In 2026, nearly one quarter (23%) of Medicare Advantage enrollees are in a special needs plan (SNP), reflecting a steady increase in recent years. Most (85%) of the net increase in Medicare Advantage enrollment between 2025 and 2026 across all plan types was among SNPs, up from 48% in the prior year.
  • More than three-quarters of SNP enrollment (78%) is in plans designed for people who are dually eligible for Medicare and Medicaid (D-SNPs), with plans for people with certain chronic conditions (C-SNPs) continuing to see a surge in enrollees in 2026 as in 2025. Enrollment in C-SNPS increased by 45% between 2025 and 2026, rising to 20% of SNP enrollment.
  • Medicare Advantage enrollment is highly concentrated among plans owned by a small number of parent organizations, with UnitedHealth Group leading the market, and, together with Humana, accounting for nearly half (46%) of all Medicare Advantage enrollees nationwide, the same as in 2025, and consistent with the pattern in prior years. However, market shares for the leading parent organizations changed with UnitedHealth Group dropping to 26% (down from 29%), and Humana increasing to 20% (up from 17%). In absolute numbers, Humana had the largest growth in enrollment, with 1.3 million more enrollees in 2026 than in 2025. In contrast, enrollment in UnitedHealth Group plans decreased by nearly 647,000 from 2025 to 2026. 

More than half of eligible Medicare beneficiaries are enrolled in Medicare Advantage in 2026.

In 2026, more than half (55%) of eligible Medicare beneficiaries – 35.2 million out of 64.2 million Medicare beneficiaries with both Medicare Parts A and B – are enrolled in Medicare Advantage plans (Figure 1). The share of Medicare beneficiaries in Medicare Advantage plans varies by state and by county (Appendix Figures 1 and 2). Medicare Advantage enrollment as a share of the eligible Medicare population has jumped from 19% in 2007 to 55% in 2026.
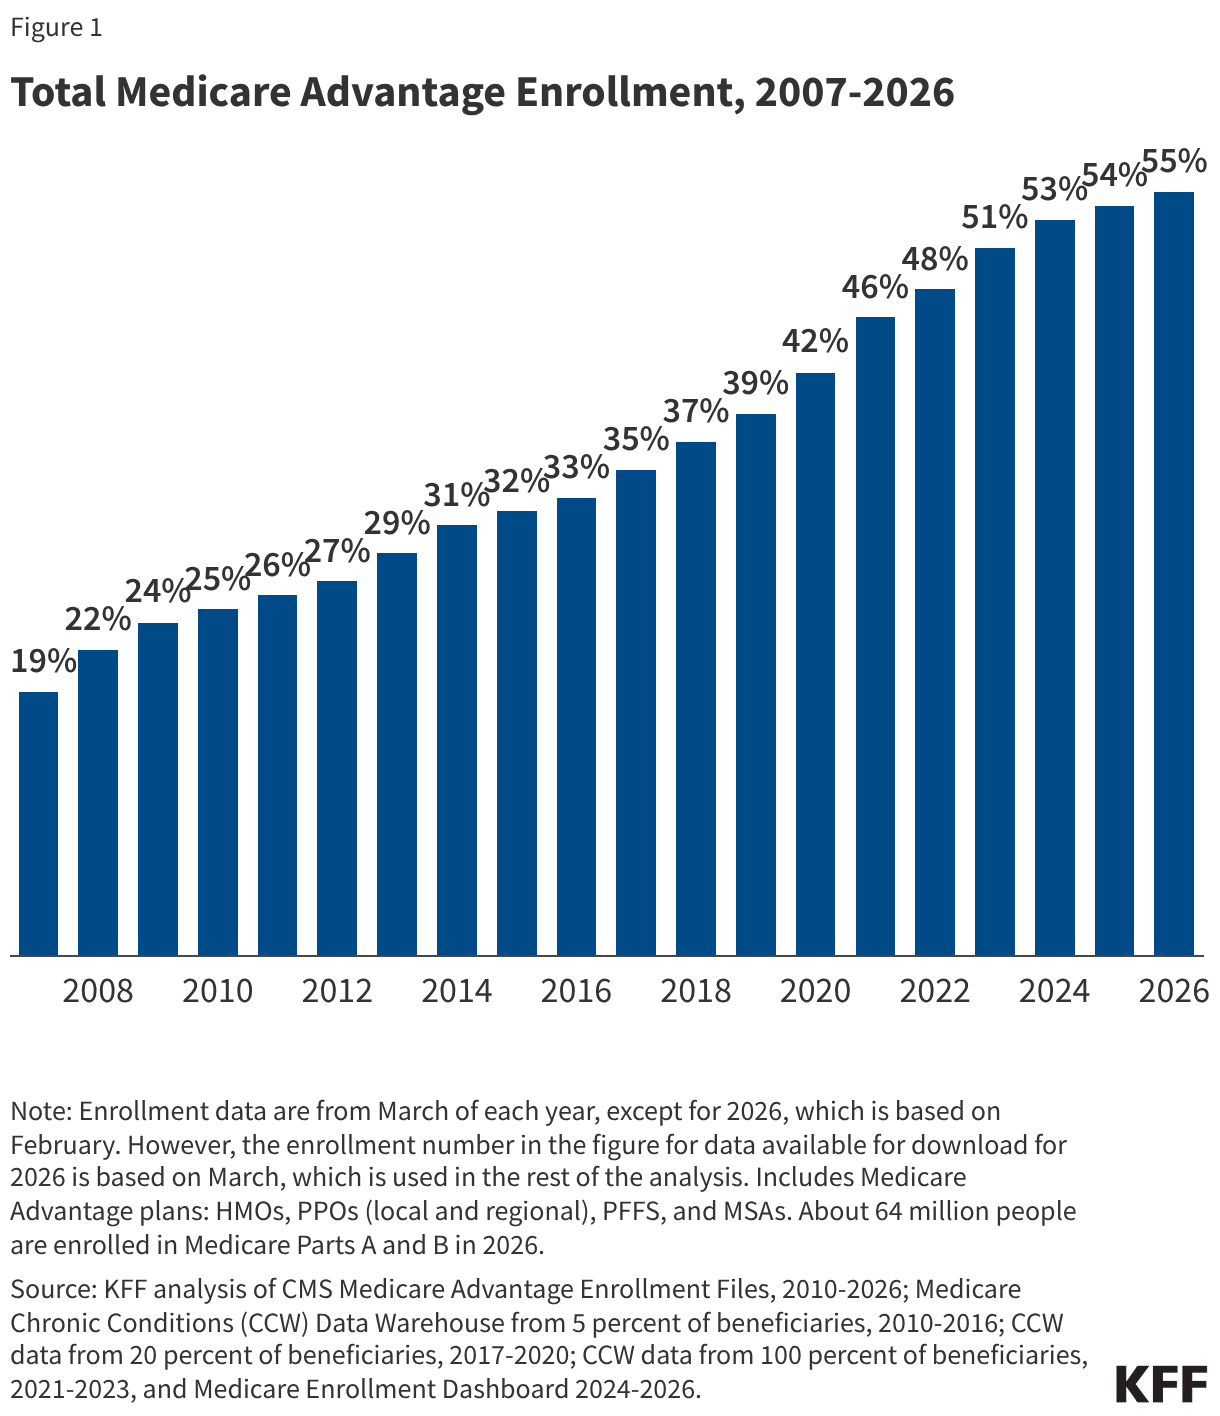
Total Medicare Advantage Enrollment, 2007-2026 (Column Chart)

Between 2025 and 2026, total Medicare Advantage enrollment grew by about 1.1 million beneficiaries, or 3% – a similar growth rate to the prior year (4%). The Congressional Budget Office (CBO) projects that the share of all Medicare beneficiaries enrolled in Medicare Advantage plans will rise to 63% by 2034 and remain at 63% for 2035 and 2036 (Figure 2).
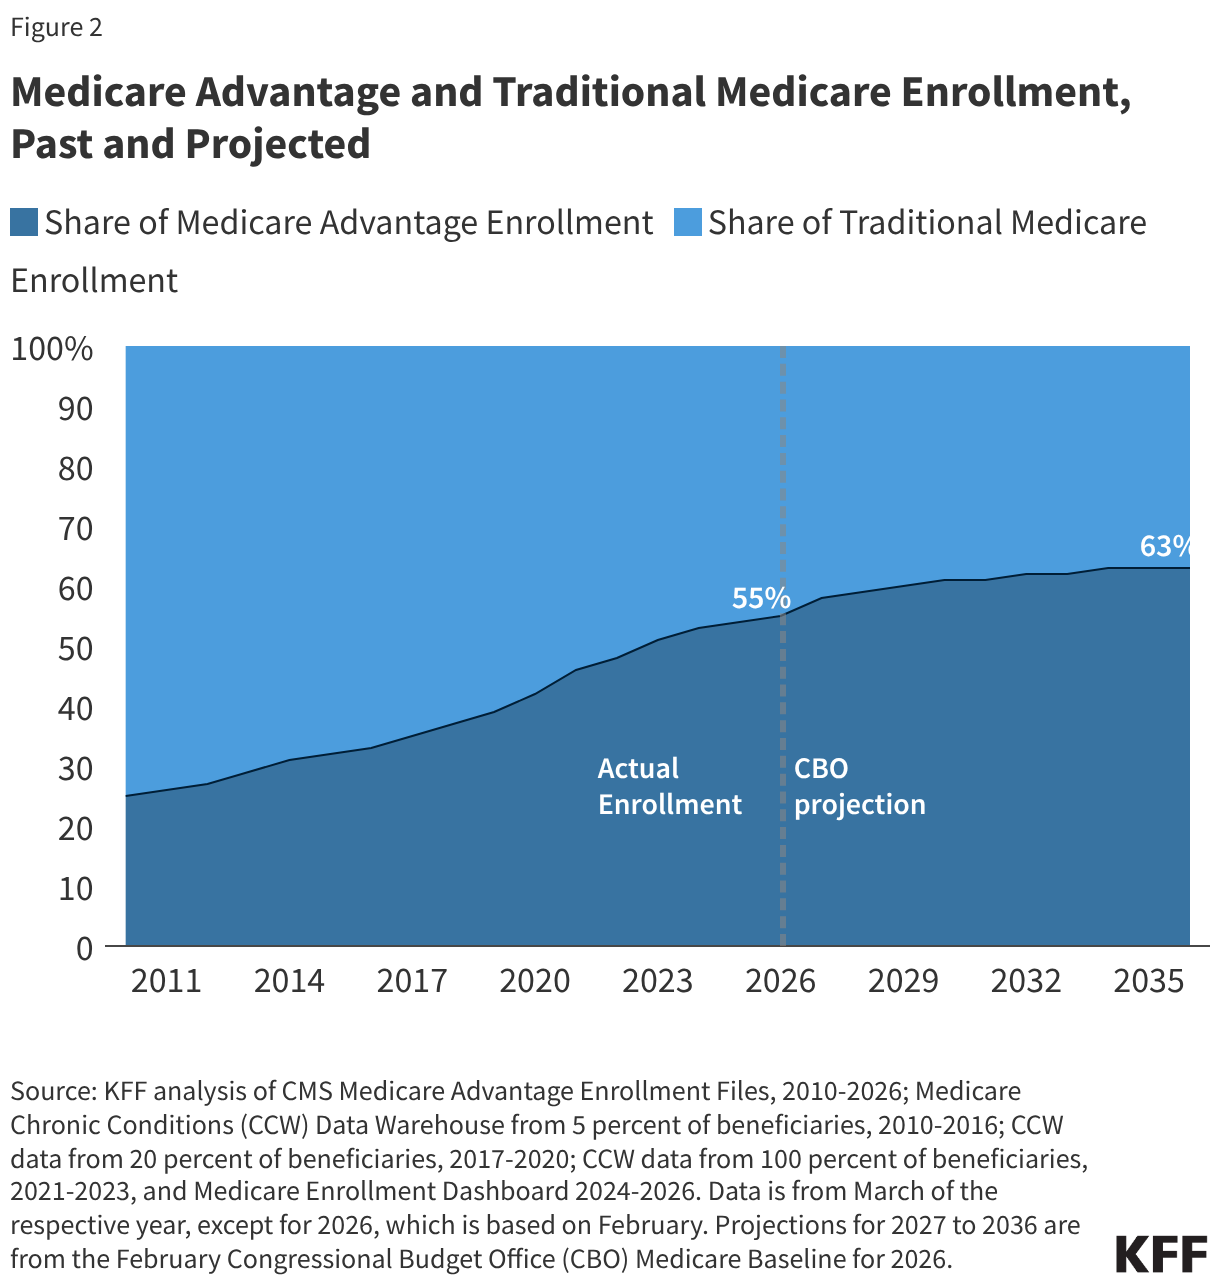
Medicare Advantage and Traditional Medicare Enrollment, Past and Projected (Area Chart)

In 2026, about six in ten Medicare Advantage enrollees are in individual plans that are open for general enrollment.

About 6 in 10 Medicare Advantage enrollees (61%), or 21.4 million people, are in plans generally available to all Medicare beneficiaries for individual enrollment (Figure 3). That is an increase of 0.2 million enrollees compared to 2025, though individual plans comprised a slightly smaller share of total Medicare Advantage enrollment in 2026 (61%) compared to 2025 (62%), and their share of enrollment has declined since 2010 when they comprised 71% of all enrollees. The decline in the share of enrollment in individual plans is due to faster enrollment growth in special needs plans (SNPs), especially since 2018.  
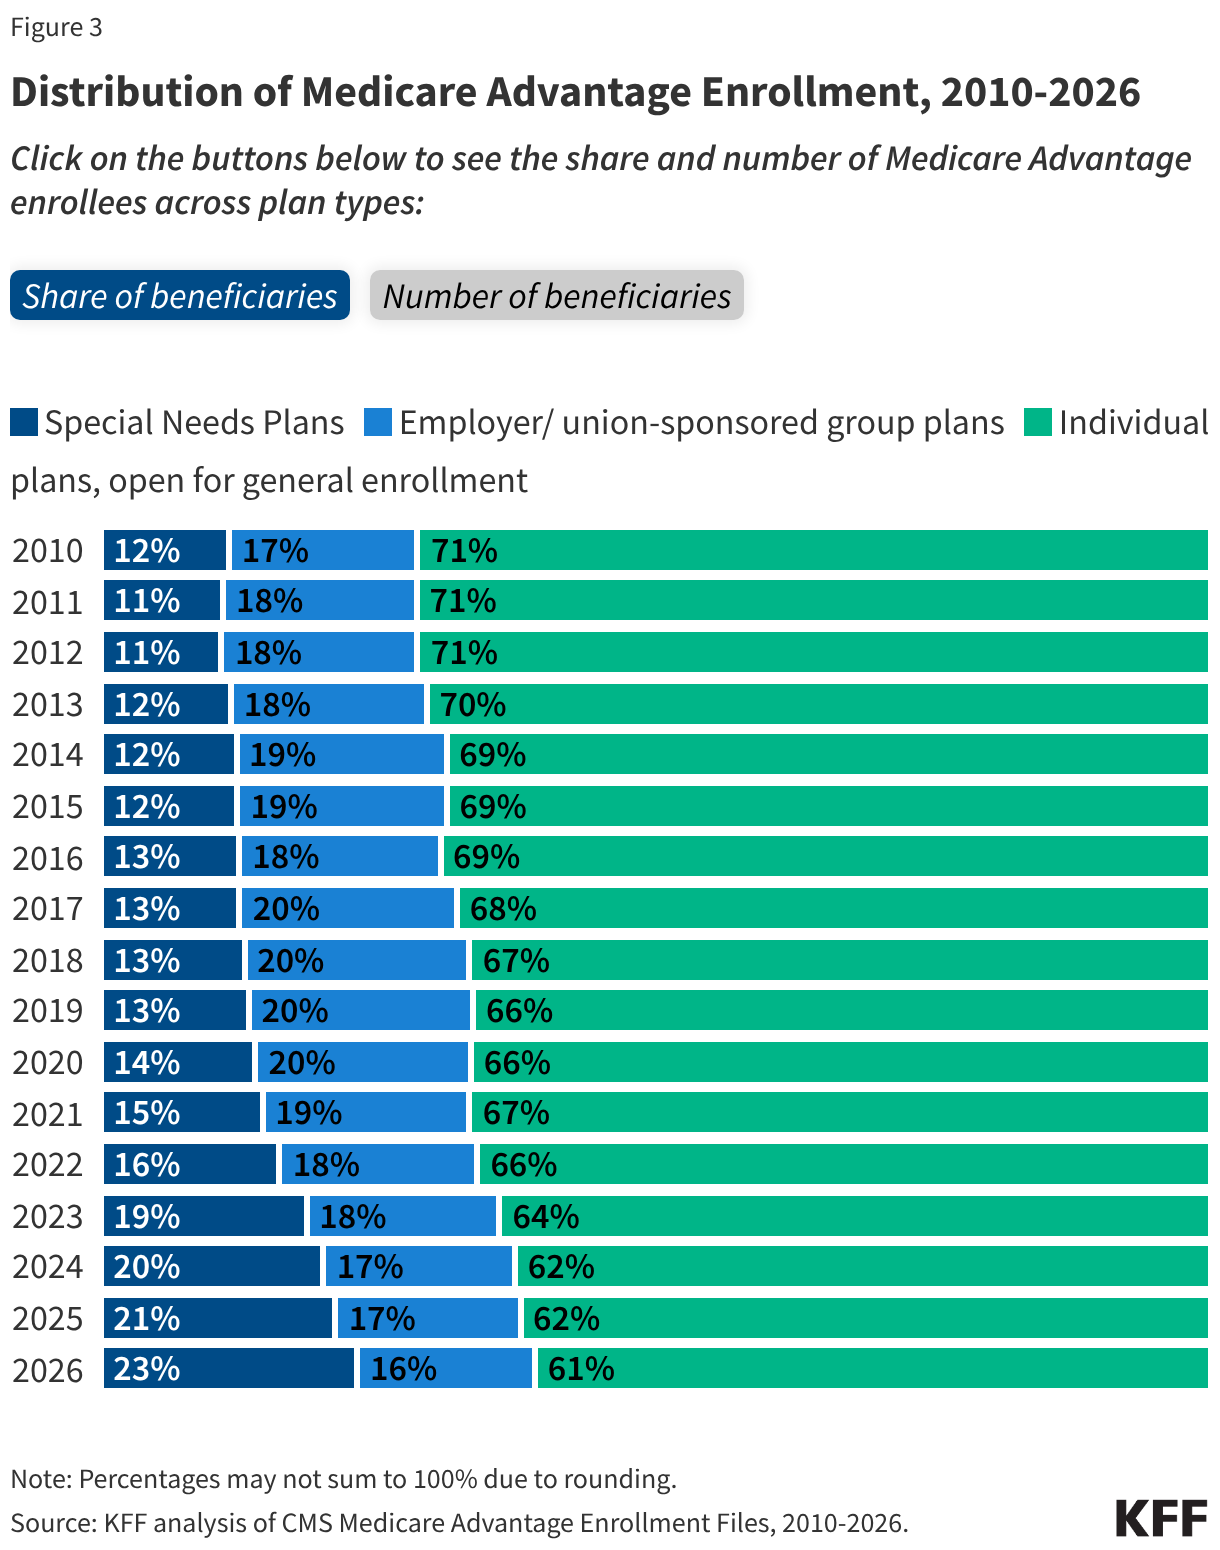
Distribution of Medicare Advantage Enrollment, 2010-2026 (Stacked Bars)

Special needs plans (SNPs) comprise a growing share of Medicare Advantage enrollment.

Nearly 8.2 million Medicare beneficiaries are enrolled in special needs plans (SNPs), an increase of more than 900,000 enrollees since 2025, and accounted for 85% of the net increase in Medicare Advantage enrollment over the last year. SNPs restrict enrollment to beneficiaries with significant or relatively specialized care needs, or who qualify because they are eligible for both Medicare and Medicaid. SNPs comprise a growing share of Medicare Advantage enrollment, accounting for 23% of enrollees in 2026 compared with 21% of enrollees in 2025 (Figure 4).
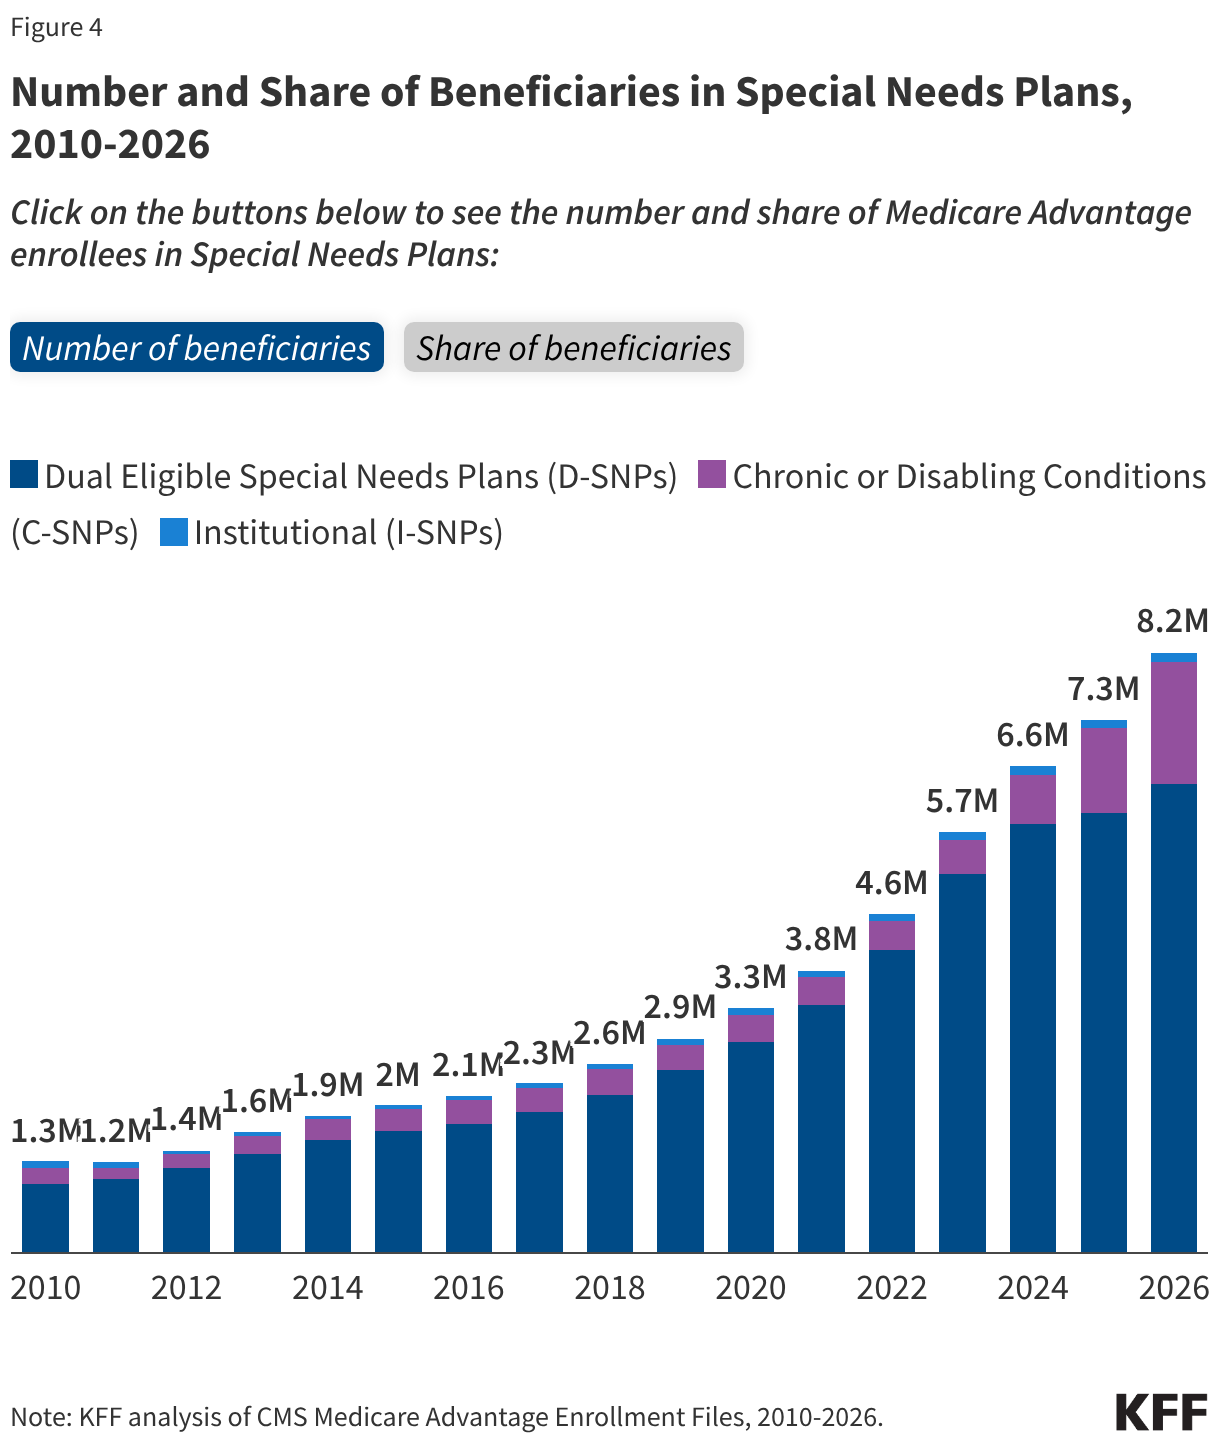
Number and Share of Beneficiaries in Special Needs Plans, 2010-2026 (Stacked column chart)

The increase in SNP enrollment is consistent with the increasing number of SNP plans available on average and more dual-eligible individuals having access to these plans since the Bipartisan Budget Act of 2018 made SNPs a permanent part of the Medicare Advantage program. Growth in SNP enrollment may also stem from the sharp increase in rebate payments, which have more than doubled since 2017 and are higher than for individual plans, which enables SNPs to offer extra benefits that are attractive to dual-eligible individuals.

Further, the Medicare Advantage Value-Based Insurance Design Model (VBID), which launched in 2017, gave plans the ability to provide additional interventions to enrollees such as reduced cost sharing and extra benefits based on their socioeconomic status (e.g., LIS eligibility), along with other targeting criteria. This meant many enrollees in SNPs, including those dually eligible for Medicare and Medicaid, may have been eligible for additional benefits. For example, plans enrolled in the model were able to offer benefits such as food and produce, assistance with utilities, and transportation for non-medical needs, among others, to a broader group of enrollees, when many of those benefits were typically reserved for enrollees who met the stricter definition of eligibility for Special Supplemental Benefits for the Chronically Ill (SSBCI). However, CMS discontinued this model in 2025 due to the “unprecedented cost” of this model, including increased rebates and increased Part D expenditures.

D-SNPs. Most SNP enrollees (78%) are in plans for beneficiaries dually enrolled in both Medicare and Medicaid (D-SNPs), a decline from 83% in 2025. While D-SNPs are designed specifically for dually-eligible individuals, among the 3.9 million dually-eligible enrollees with full benefits enrolled in Medicare Advantage plans, 28% were enrolled in Medicare Advantage plans that are generally available to all beneficiaries (not designed specifically for the dually-eligible population).

C-SNPs. Another 20% of SNP enrollees are in plans for people with severe chronic or disabling conditions (C-SNPs) – an increase from 16% in 2025. C-SNP enrollment in 2026 (about 1.7 million people) is 45% higher than it was in 2025 – an increase of about 518,000 enrollees. Nearly all (97%) C-SNP enrollees are in plans for people with diabetes or cardiovascular conditions in 2026, the same as in 2025.

I-SNPs. And 2% of SNP enrollees in 2026 are in plans for beneficiaries requiring a nursing home or institutional level of care (I-SNPs), the same as 2025. Enrollment in I-SNPs increased slightly in 2026 124,000 enrollees, an increase of about 9,000 enrollees since 2025.

SNP enrollment varies across states. In the District of Columbia and Puerto Rico, SNP enrollees comprise about half of all Medicare Advantage enrollees (51% in DC and 49% in PR). In eleven states, SNP enrollment accounts for at least a quarter of Medicare Advantage enrollment: 46% in MS, 40% in AR, 37% in NY, 36% in LA, 33% in FL, 32% in SC, 30% in GA, 27% in OK and AL, 26% in CT, and 26% in RI. In the remaining 39 states, fewer than a quarter of Medicare Advantage enrollees are in SNPs, including Alaska and Vermont, which have no SNP enrollment.

Enrollment in a D-SNP comprises the largest share of enrollment in SNPs in all states except New Hampshire where C-SNP enrollment is higher, though overall SNP enrollment only represents 2% of Medicare Advantage enrollment in New Hampshire. C-SNP enrollment represents a relatively large share of Medicare Advantage SNP enrollment in Illinois, Utah, South Carolina, Delaware, Nevada, and Oregon, where 40% or more of SNP enrollment is in C-SNPs.

Slightly less than one in five (16% or about 5.7 million) Medicare Advantage enrollees are in a group plan offered to retirees by an employer or union.

Group enrollment as a share of total Medicare Advantage enrollment is 16%, the lowest share since 2010, though it has generally fluctuated between 17% and 20% of enrollment. At the same time, the number of enrollees has increased from 1.8 million in 2010 to 5.7 million in 2026. The 2026 enrollment in group plans is a slight decrease from 2025 (a decrease of about 31,000 enrollees), the first time since 2010 that enrollment in this type of plan has declined year-to-year (Figure 5). With a group plan, an employer or union contracts with an insurer and Medicare pays the insurer a fixed amount per enrollee to provide benefits covered by Medicare. For example, 13 states provided health insurance benefits to their Medicare-eligible retirees exclusively through Medicare Advantage plans in 2024.
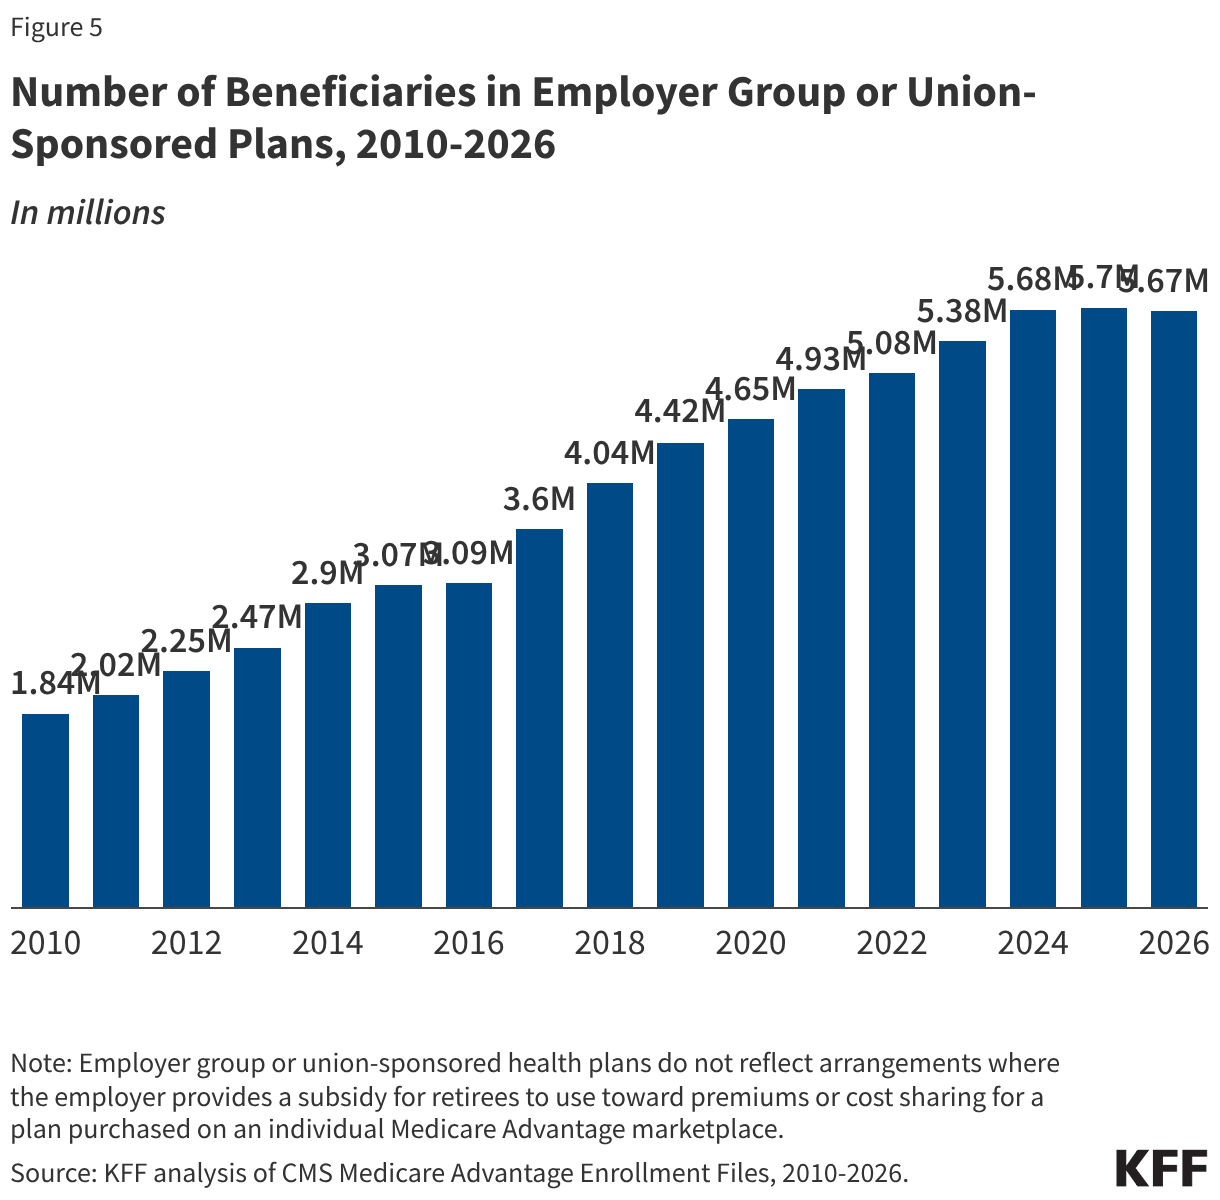
Number of Beneficiaries in Employer Group or Union-Sponsored Plans, 2010-2026 (Column Chart)

As with other Medicare Advantage plans, employer and union group plans may provide additional benefits and/or lower cost sharing than traditional Medicare and are eligible for bonus payments if they obtain required quality scores. The employer or union (and sometimes the retiree) may also pay an additional premium for these supplemental benefits. Group enrollees comprise a quarter or more of Medicare Advantage enrollees in seven states: 100% in AK, 60% in VT, 34% in MI, 31% in NJ, 28% in MD and WV, and 25% in IL.

Medicare Advantage enrollment is highly concentrated among a small number of parent organizations.

The average Medicare beneficiary is able to choose from Medicare Advantage plans offered by 8 parent organizations in 2026, the same as in 2025 and 2024, and nearly three in ten (29%) can choose among Medicare Advantage plans offered by 10 or more parent organizations.

UnitedHealth Group and Humana account for nearly half of all Medicare Advantage enrollees nationwide in 2026.

Despite most beneficiaries having access to plans operated by several parent organizations, Medicare Advantage enrollment is highly concentrated among a small number of parent organizations (Figure 6). UnitedHealth Group Inc. accounts for 26% of all Medicare Advantage enrollment in 2026 (a decline from 29% in 2025), or 9.3 million enrollees. Humana Inc. accounts for 20% of all Medicare Advantage enrollment in 2026 (an increase from 17% in 2025), or 7 million enrollees. Together, UnitedHealth Group Inc. and Humana Inc. account for nearly half (46%) of all Medicare Advantage enrollees nationwide, the same share as in 2025. In more than a quarter of counties (28% or 889 counties), these two organizations account for at least 75% of Medicare Advantage enrollment. These counties include East Baton Rouge (Baton Rouge), LA (81%), Travis County (Austin), TX (78%), Jackson County (Kansas City), MO (76%), and Palm Beach, Florida (75%).

Three other parent organizations comprise more than 5% of Medicare Advantage enrollment: CVS Health Corporation (12%), Kaiser Foundation Health Plan Inc. (6%), and Elevance Health Inc, (5%). (In contrast, as of 2025, CVS Health and Centene Corporation dominate the market for stand-alone prescription drug plans (PDP) that supplement traditional Medicare, with both organizations accounting for just over half of enrollment in PDPs).
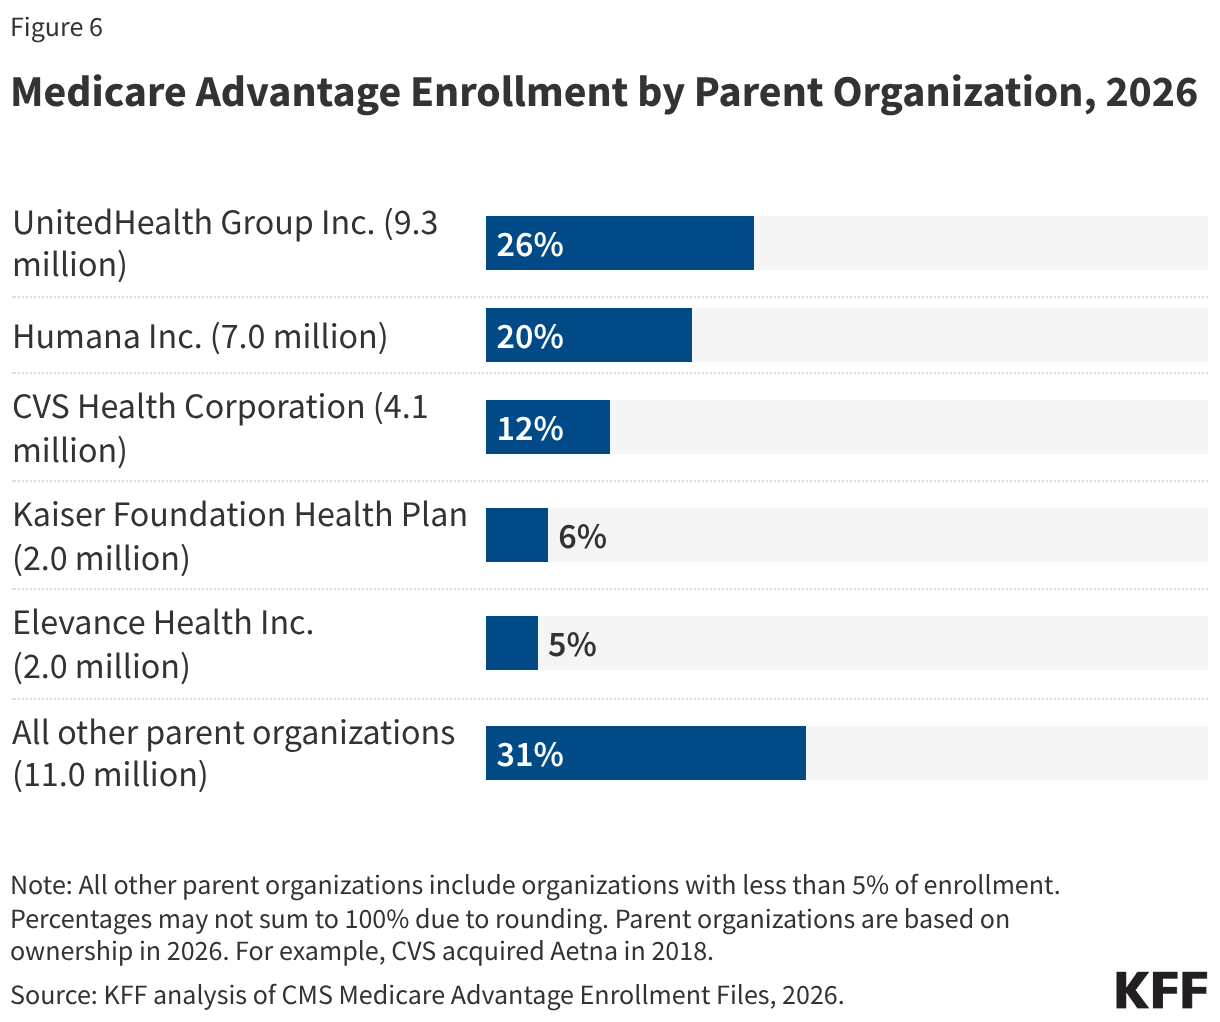
Medicare Advantage Enrollment by Parent Organization, 2026 (Bar Chart)

Humana and Kaiser Permanente were the only large insurers to increase enrollment from 2025 to 2026.

In absolute numbers, Humana had the largest growth in enrollment, with 1.3 million more beneficiaries enrolled in a plan sponsored by Humana in March 2026 than in March 2025 (Figure 7). Of the largest insurers (5% of enrollment or more), Kaiser Permanente had the second largest growth in enrollment, with an increase of nearly 87,000 beneficiaries between March 2025 and March 2026. However, some smaller insurers had even larger growth – Devoted Health had an increase of nearly 258,000, SCAN Group had an increase of 136,000, and Aware Integrated had an increase of 89,000 beneficiaries between March 2025 and March 2026 (data not shown).

In contrast, enrollment in UnitedHealth plans declined, decreasing by nearly 647,000 beneficiaries between March 2025 and March 2026, and Elevance had the second largest enrollment drop, losing 346,000 beneficiaries, while enrollment in CVS plans declined by nearly 29,000.
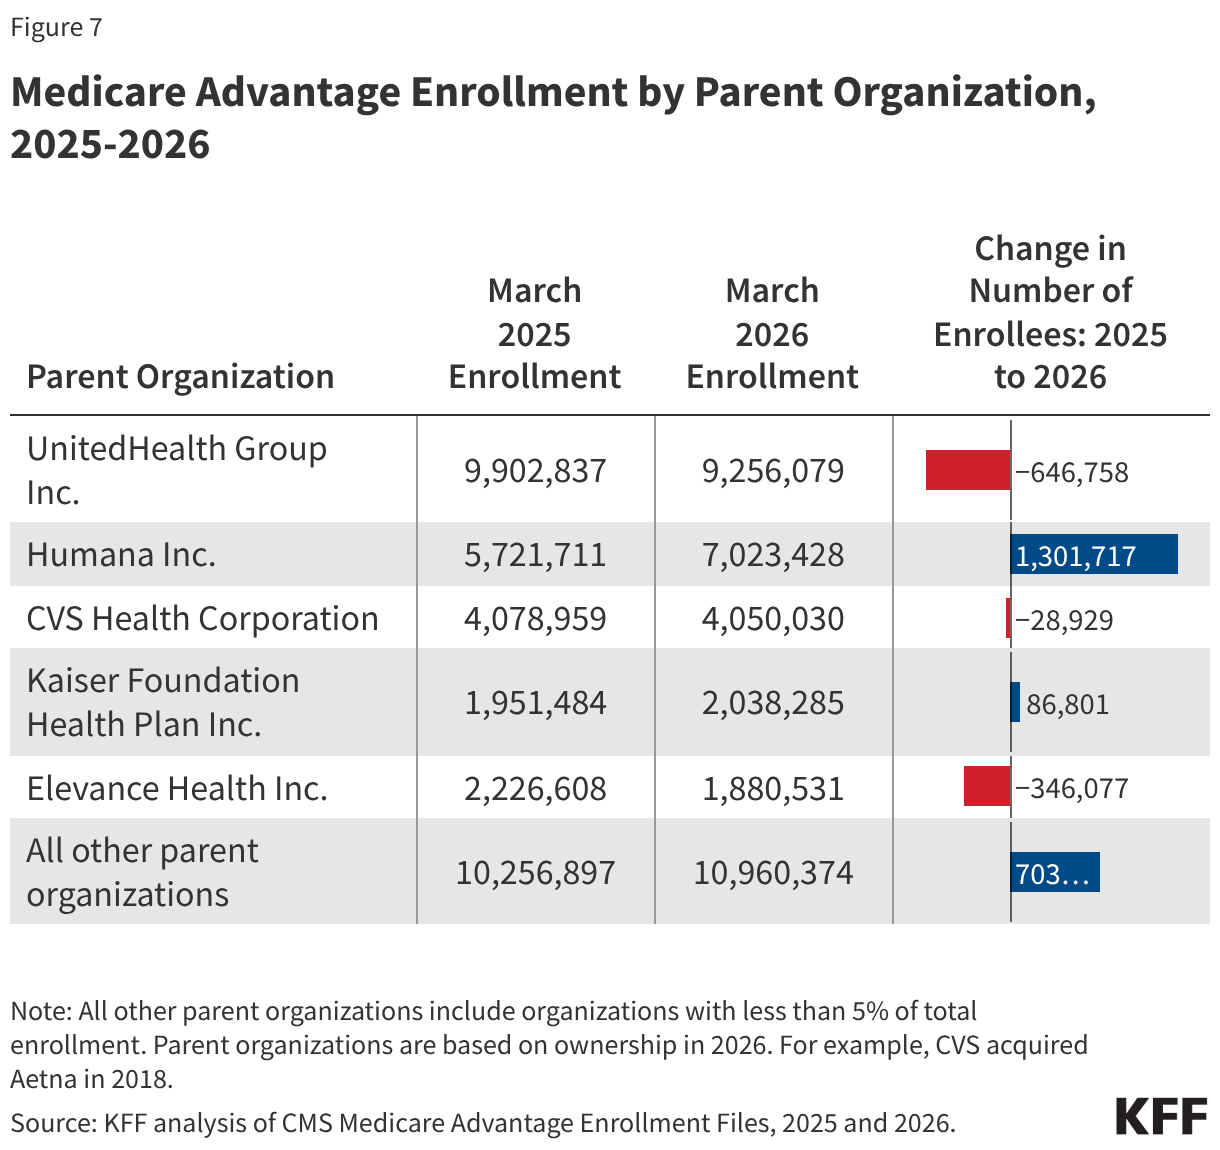
Medicare Advantage Enrollment by Parent Organization, 2025-2026 (Table)

Methods

This analysis uses data from the Centers for Medicare & Medicaid Services (CMS) Medicare Advantage Enrollment, Benefit and Landscape files for the respective year. KFF uses the Medicare Enrollment Dashboard for enrollment data for March 2024-2026, and the CMS Chronic Conditions Data Warehouse Master Beneficiary Summary File (MBSF) for March for earlier years. For other analyses of enrollment in this brief, KFF uses March data; enrollment data is only provided for plan-county combinations that have at least 11 beneficiaries; thus, this analysis excludes approximately 400,000 individuals who reside in a county where county-wide plan enrollment does not meet this threshold. Trend analysis begins in 2007 because that was the earliest year of data that was based on March enrollment. Data from the Medicare enrollment dashboard (used to calculate penetration rates) may change retroactively as CMS updates and reconciles administrative enrollment records. As a result, historical enrollment counts and penetration rates may differ from earlier downloads of the same data.

KFF calculates the share of eligible Medicare beneficiaries enrolled in Medicare Advantage, meaning they must have both Part A and B coverage. In previous years, KFF calculated the share of Medicare beneficiaries enrolled in Medicare Advantage by including Medicare beneficiaries with either Part A and/or B coverage. We modified our approach in 2022 to estimate the share enrolled among beneficiaries eligible for Medicare Advantage who have both Medicare Part A and Medicare B.

Additionally, in previous years, KFF had used the term Medicare Advantage to refer to Medicare Advantage plans as well as other types of private plans, including cost plans, PACE plans, and HCPPs. However, cost plans, PACE plans, and HCPPs are excluded from this analysis in addition to MMPs. In this analysis, KFF excludes these other plans as some may have different enrollment requirements than Medicare Advantage plans (e.g., may be available to beneficiaries with only Part B coverage) and in some cases, may be paid differently than Medicare Advantage plans. These exclusions are reflected in all data displayed trending back to 2007.

Beginning with the analysis of 2025 Medicare Advantage enrollment, KFF has relied on the parent organization field reported to CMS to identify plans sponsored by the same insurer. Previously, KFF had supplemented these data with publicly available information about acquisitions, mergers, and business relationships. The previous approach led to fewer total plan sponsors.

Medicare projections for 2027-2036 are from the February Congressional Budget Office (CBO) Medicare Baseline for 2026. Using the CBO baseline, Medicare enrollment is based on individuals who are enrolled in Part B, which is designed to include only individuals who are eligible for Medicare Advantage and exclude those who only have Part A only (~5.7 million people in 2026) and cannot enroll in Medicare Advantage. However, it may include some individuals who have Part B only and also are not eligible for Medicare Advantage.

Enrollment counts in publications by firms operating in the Medicare Advantage market, such as company financial statements, might differ from KFF estimates due to inclusion or exclusion of certain plan types, such as SNPs or employer group health plans.

Appendix
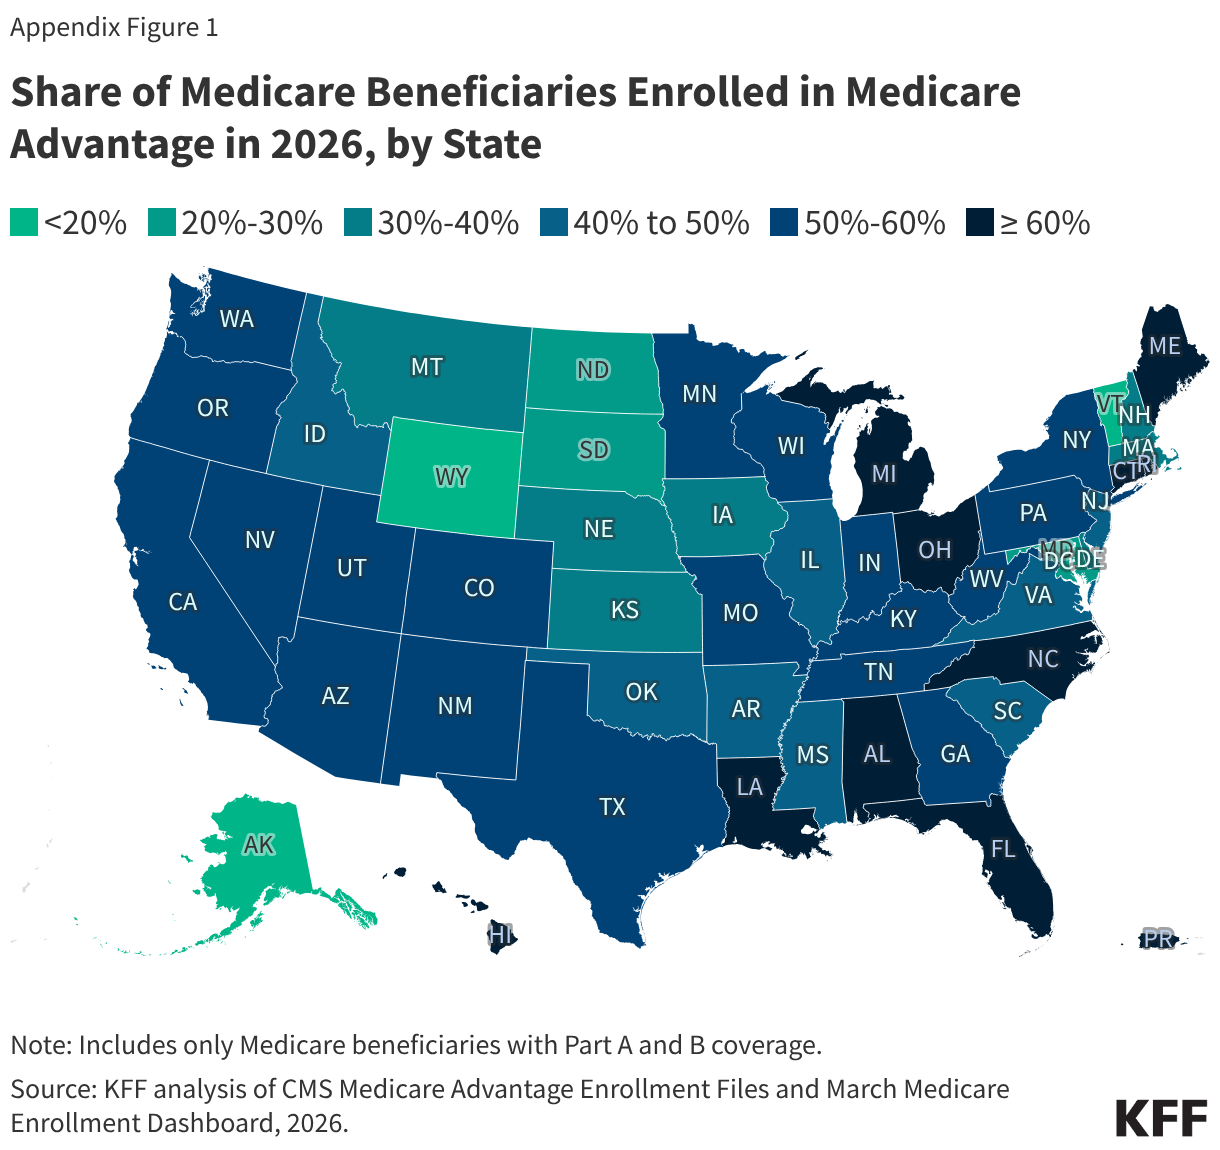
Share of Medicare Beneficiaries Enrolled in Medicare Advantage in 2026, by State (Choropleth map)
Share of Medicare Beneficiaries Enrolled in Medicare Advantage in 2026, by County (Choropleth map)

Meredith Freed, Jeannie Fuglesten Biniek, Nancy Ochieng, and Tricia Neuman are with KFF. Anthony Damico is an independent consultant.


Elimination of Federal Diversity Initiatives: Updates and Current Status

Published: Jun 4, 2026

Editorial Note: This represents an update of an earlier analysis: Elimination of Federal Diversity Initiatives: Implications for Racial Health Equity

It has now been over a year since President Trump signed executive orders eliminating federal diversity, equity, inclusion, and accessibility (DEIA) programs and related initiatives, reshaping policies and priorities across federal agencies, research, and education. Additionally, the Trump administration’s workforce reshaping initiatives, including reductions in force, the Deferred Resignation Program, early retirement incentives and a hiring freeze have led to major declines in the federal workforce which have reduced resources available to support efforts to address disparities. While some efforts have been halted or modified by court rulings, the Trump administration has continued to take steps to remove staff, programs, funding, data collection, and other activities tied to concepts of diversity, equity, or disparities. Together, these actions signal a significant shift in federal approaches to addressing inequities and may have broad implications for efforts to monitor and address disparities in health and health care, as well as for the diversity of the workforce, including in health care.

This brief provides an update on the status of the administration’s actions to eliminate DEI-related initiatives one year later and examines emerging impacts and implications for racial health disparities.

Reductions to Federal Agency Staff and Programs

Federal workforce reductions have led to the elimination or scaling back of programs that support data collection, research, and interventions that have historically included a focus on addressing disparities or groups at higher risk of poor health outcomes. Since January 2025, the Trump administration’s workforce reshaping initiatives have led to significant federal workforce declines, with more than 420,000 people separating from the federal workforce as of May 14, 2026. Within the Department of Health and Human Services (HHS), staffing losses have exceeded 20,000 employees since January 2025. At the Centers for Disease Control and Prevention (CDC), an estimated 15% of the workforce, or about 3,000 employees, have departed, with some reports suggesting even larger reductions. With these reductions, many programs that support research and public health interventions appear to have been terminated. Although the full scope of program cutbacks is unclear due to the lack of a comprehensive public record, staffing reductions across agencies have left key programs understaffed or unable to maintain core functions, including efforts focused on addressing health disparities and advancing health equity. For example:

  • Reporting suggests that layoffs within the CDC’s Division of Reproductive Health in late March and early April reduced the workforce by about two-thirds, disrupting multiple programs focused on maternal and infant health, an area of health with longstanding disparities. These cuts included the elimination of the Pregnancy Risk Assessment Monitoring System (PRAMS), a primary source of data on health behaviors and outcomes before, during, and after pregnancy that has been widely used to study maternal mortality, including disparities, leaving its future uncertain.
  • At HHS, the Office of Climate Change and Health Equity was removed from the agency’s website, and its staff were reportedly placed on administrative leave. Staffing reductions within the CDC’s Division of Environmental Health Science and Practice also led to the elimination of the Environmental Public Health Tracking Program, which monitored data on issues such as cancer clusters and weather-related illnesses. Together, these changes may limit federal capacity to monitor and address environmental and climate-related health disparities, particularly among low-income communities and communities of color that are often disproportionately exposed to environmental hazards and extreme weather events.
  • The elimination of the National Survey on Drug Use and Health team halted a key federal data source on substance use and mental health trends, while CDC staff supporting the National Youth Tobacco Survey were also eliminated. Both surveys have historically been used to assess differences in behavioral health and tobacco use across populations and to help guide prevention and treatment efforts for groups disproportionately affected by these issues.

Elimination of Grants and Research Initiatives

Efforts to eliminate DEI across the federal government have reduced support for research related to disparities, including through funding cuts, changes to grant review and award processes, and the loss of leadership and infrastructure that support clinical trials and participation. Federal agencies have reduced or eliminated funding for research initiatives that included DEI-related goals or focused on specific populations, and grant review processes have been revised to flag or exclude applications containing DEI-related terms or focus areas including discrimination, diversity, equity, and race. For example, the recently formed and now defunct Department of Government Efficiency (DOGE) was tasked with auditing and canceling DEI-related federal research grants. Recent deposition hearings indicate that staff members used ChatGPT to propose cuts to roughly 1,400 grants under the National Endowment for the Humanities, including examples that were not related to DEI. In addition to the grants reviewed under DOGE, broader administrative actions led to the termination of more than 2,300 National Institute of Health (NIH) grants by late June 2025, with nearly 1,100 grants remaining terminated as of May 4, 2026. One study found that the National Institute of Minority Health and Health Disparities lost both the largest share of grants and the largest share of funding across all NIH institutes and centers. Research shows that grant terminations were more likely to impact American Indian or Alaskan Native (AIAN), Asian, Black, Hispanic or Native Hawaiian or Pacific Islander (NHPI) researchers compared to White researchers. These actions also affected 160 NIH-funded clinical trials, more than half of which (57%) included project terms related to racial and ethnic minority populations, such as Black, Latino, Indigenous, Asian, and other historically underserved groups. At the same time, the loss of research leadership and staff has disrupted the research pipeline and contributed to additional grant terminations. HIV research has been particularly impacted. Reporting indicates that at least 145 NIH-funded HIV research grants, totaling nearly $450 million, were terminated in early 2025, including studies focused on HIV prevention, access to pre-exposure prophylaxis (PrEP), and populations disproportionately affected by HIV, which include groups of color. A newly proposed rule issued by the Office of Management and Budget (OMB) would revise federal grant requirements by increasing political review of awards, requiring alignment with presidential priorities, and creating new mechanisms for modifying or terminating existing funding, with an emphasis on prohibiting federal support for programs, funding preferences, or award requirements that advance DEI efforts. If finalized, the proposal could expand federal grantmaking agencies’ authority to review and terminate awards deemed inconsistent with the administration’s interpretation of civil rights laws and federal priorities, which may affect research and programs designed to address racial, ethnic, gender, and other disparities.

Elimination of Public Information and Resources

Efforts to eliminate DEI across the federal government have also reduced the availability and integrity of public information and data, including through the suspension of national surveys, the removal of DEI-related data elements, and changes to climate data and evidence. As previously noted, several national surveys were suspended, delayed, or scaled back, limiting the availability of timely population-level data. These include the Pregnancy Risk Assessment Monitoring System (PRAMS) and the National Survey on Drug Use and Health (NSDUH). There are also reports that the National Intimate Partner and Sexual Violence Survey and the National Youth Tobacco Survey (NYTS) may have also been eliminated, however, their official status remains unclear. These surveys have historically provided data used to identify disparities and inform public health policy and interventions. In addition, key surveys and data systems removed or modified questions and data elements related to race, ethnicity, gender identity, sexual orientation, and other demographic measures, reducing the ability to measure differences across populations. Some publicly available datasets were also modified or taken offline, limiting access for researchers, policymakers, and the public, while some federal websites removed or archived reports, dashboards, and tools that previously highlighted disparities or equity-focused analyses. Climate-related data and resources were similarly removed, reframed and misrepresented, or made more difficult to access. For example, the Trump administration determined that official government websites would no longer host national climate assessments, including the most recent assessment released in 2023, which found that climate change disproportionately affects the health, livelihoods, and security of people of color, with Indigenous populations at particular risk. In addition, concerns have been raised about the scientific rigor and peer review process of the Climate Working Group report recently released under the administration.

Education and Workforce

Amid the executive orders, threats by the Trump administration to withdraw funding from schools with DEI programs, and charges from the Equal Employment Opportunity Commission (EEOC) for discrimination against White people, concerns have grown about the potential impacts on diversity among students and the future workforce. Early last year, the Department of Education issued guidance, commonly referred to as the “Dear Colleague” letter, directing schools and other entities receiving federal education funding to stop using what it described as “racial preferences” in admissions, programming, and other activities. This followed the Supreme Court’s 2023 decision ending race-conscious admissions, which led to a shift in enrollment patterns across higher education institutions, with declines in the share of students of color at highly selective universities. Research also suggests that the ruling has already contributed to declines in the number of Black, Hispanic, and AIAN students entering medical school, raising concerns about the future diversity of the physician workforce. These trends may further exacerbate existing disparities in representation. KFF analysis shows that Hispanic, Black, AIAN, and NHPI people remain underrepresented among physicians relative to their share of the population, with the largest gap among Hispanic people, who comprise 20% of the U.S. population but only 7% of the physician workforce. More broadly, the EEOC has increasingly emphasized enforcement related to alleged discrimination against White workers, which some argue could discourage workplace diversity initiatives. In addition, broader immigration restrictions and enforcement actions may further affect workforce diversity, particularly in health care and research fields that rely heavily on immigrant workers and internationally trained professionals.

In some cases, implementation of DEI-related cuts has been temporarily halted or mitigated by lawsuits and congressional action. As of April 2026, Congress has rejected many of the Trump administration’s proposed reductions to federal health programs through the FY 2026 appropriations process. For example:

  • The legislation provided HHS with approximately $116 billion in funding, about $33 billion more than proposed in President Trump’s FY 2026 budget request, including increases for several public health and behavioral health programs, such as reproductive and community health programs, that support populations disproportionately affected by poor health outcomes, including people of color and lower-income groups.
  • It also maintained the Substance Abuse and Mental Health Services Administration (SAMHSA) as an independent agency and increased SAMHSA funding by $65 million to approximately $7.4 billion, despite earlier proposals to reduce funding by roughly $1 billion. The legislation also included guardrails intended to ensure that SAMHSA funds are distributed as appropriated, preserving support for mental health and substance use programs that often serve low-income and underserved communities.
  • Similarly, Congress maintained CDC funding at approximately $9.2 billion, rather than the nearly 50% reduction proposed in the administration’s FY 2026 budget request, and directed HHS to maintain staffing levels needed to carry out CDC programs, although the agency’s Social Determinants of Health program was eliminated.
  • The legislation also preserved funding for reproductive health programs, including Title X and the Teen Pregnancy Prevention Program, and increased investments in maternal health programs across HRSA, CDC, and NIH, which have historically focused on addressing longstanding racial disparities in maternal and infant health outcomes.
  • In addition, while the administration proposed substantial reductions to NIH funding, Congress ultimately approved increased funding for the agency, and several court challenges temporarily halted some funding cuts and grant terminations, which had a noted focus on DEI-related research.

Separate legal challenges have also limited implementation of some workforce and education-related actions. Federal courts and Congress blocked or delayed aspects of the Trump administration’s workforce reduction efforts, including rulings against certain reductions in force and layoffs implemented during agency restructuring efforts. Courts also blocked implementation of the Department of Education’s “Dear Colleague” guidance related to race-conscious practices in schools, and the Department later withdrew the guidance following legal challenges and court rulings. These actions suggest that the scope and long-term effects of the administration’s policies may continue to evolve as litigation and congressional oversight proceed.

U.S. International Family Planning & Reproductive Health: Requirements in Law and Policy

Published: Jun 2, 2026

This fact sheet summarizes the major statutory requirements and policies pertaining to U.S. global family planning/reproductive health (FP/RH) efforts over time and identifies those currently in effect. These laws and policies collectively serve to direct how U.S. funds are spent, to where and which organizations funds are provided, and generally shape the implementation and define the scope of U.S. global FP/RH activities. It includes U.S. laws and annual requirements enacted by Congress through appropriations bills (statutory provisions) as well as executive branch policies and guidance specific to FP/RH (policy provisions). Each category lists provisions in chronological order.

Since early 2025, the Trump administration has frozen or eliminated funding for most FP/RH activities, although Congress has continued to appropriate funding for this work. See the KFF fact sheet of the status of FP/RH efforts.

Table 1

Statutory Requirements and Policies for U.S. Global FP/RH Efforts (as of FY 2026)

Provision (Year First Instituted)Issue(s)Applies toStatus
STATUTORY
Helms Amendment (1973)
Prohibits the use of foreign assistance to pay for the performance of abortion as a method of family planning or to motivate or coerce any person to practice abortion. Note: meaning of “motivate” clarified by Leahy Amendment (1994); see below.
Abortion

All foreign assistance authorized under the Foreign Assistance Act of 1961(FAA); all funds under State-Foreign Operations Appropriations (State-Foreign Ops.)Yes, in effect.
Permanent law, amendment to the FAA.
Also included in annual State-Foreign Ops.
Involuntary Sterilization Amendment (1978)
Prohibits the use of funds to pay for involuntary sterilizations as a method of family planning or to coerce or provide a financial incentive to anyone to undergo sterilization.
Voluntarism/
Informed Choice & Consent; Incentives; Involuntary Sterilization
All foreign assistance authorized by the FAA of 1961; all foreign assistance funds under State-Foreign Ops.Yes, in effect.
Permanent law, amendment to the FAA.
Also included in annual State-Foreign Ops.
Peace Corps Provision (1978)
Prohibits Peace Corps funding from paying for an abortion for a Peace Corps volunteer or trainee; beginning in FY 2015, allows for payment in cases where the life of the woman is endangered by pregnancy or in cases of rape or incest.1
AbortionAll Peace Corps fundingYes, in effect.
Included under the “Peace Corps” heading of the State-Foreign Ops.
Biden Amendment (1981)
States that funds may not be used for biomedical research related to methods of or the performance of abortion or involuntary sterilization as a means of family planning.
Abortion; Involuntary SterilizationAll foreign assistance authorized by the FAA of 1961; all foreign assistance funds under State-Foreign Ops.Yes, in effect.
Permanent law, amendment to the FAA.
Also included in annual State-Foreign Ops.
Siljander Amendment (1981)
Prohibits the use of funds to lobby for or against abortion. When initially introduced, the amendment prohibited only lobbying for abortion, but in subsequent years Congress modified the language to include lobbying against abortion as well.
AbortionAll funds under State-Foreign Ops.
 
Yes, in effect.
Included in annual State-Foreign Ops.
DeConcini Amendment (1985)
Requires that U.S. funds be provided to organizations that offer, either directly or through referral to, information about access to a broad range of family planning methods and services. See Livingston-Obey Amendment (1986) below.
Voluntarism/
Informed Choice
All FP funds under State-Foreign Ops.Yes, in effect.
Included in annual State-Foreign Ops.
Kemp-Kasten Amendment (1985)
Prohibits funding any organization or program, as determined by the President, that supports or participates in the management of a program of coercive abortion or involuntary sterilization.
UNFPA Funding; Abortion; Voluntarism/
Informed Choice & Consent; Involuntary Sterilization
All funds under State-Foreign Ops. as well as unobligated balances from prior appropriations actsYes, in effect.
Included in annual State-Foreign Ops.2 each year; Presidents determined that it applied to UNFPA in FY85-FY92, FY02-FY08, FY17-FY20, FY25.
Involuntary Sterilization and Abortion Provision (1985)
Specifies that U.S. foreign assistance funding could be withheld from a country or organization if the president certifies that the use of such funds would violate key provisions of the FAA of 1961 related to abortion or involuntary sterilization (namely the Helms, Biden, and Involuntary Sterilization Amendments).
Voluntarism/
Informed Choice & Consent; Incentives; Abortion; Involuntary Sterilization
All foreign assistance funds under State-Foreign Ops.
 
Yes, in effect.
Included in annual State-Foreign Ops.
Livingston-Obey Amendment (1986)
Prohibits discrimination by the U.S. government against organizations that offer only “natural family planning” for religious or conscientious reasons when the U.S. government is awarding related grants. All such applicants must comply with the requirements of the DeConcini Amendment (1985).
Voluntarism/
Informed Choice
All FP funds under State-Foreign Ops.
 
Yes, in effect.
Included in annual State-Foreign Ops.
Leahy Amendment (1994)
Clarifies Helms Amendment (1973) language that uses the term “motivate” by stating that “motivate” shall not be construed to prohibit, where legal, the provision of information or counseling about all pregnancy options.
Abortion; Voluntarism/
Informed Choice
All authorizing and appropriating legislation related to the State Dept., foreign operations, and related programsYes, in effect.
Included in annual State-Foreign Ops.
Timing of Release of UNFPA Contribution Funds (1994)
Not more than half of funding designated for the U.S. contribution to UNFPA is to be released before a particular date (varies by fiscal year).
UNFPA FundingFunds made available to UNFPANo, not in effect.
Sometimes included in annual State-Foreign Ops.
Conditions on Availability of UNFPA Funds (UNFPA Segregated U.S. Contribution Account; UNFPA Does Not Fund Abortions; Prohibition on the Use of U.S. Funds in China by UNFPA) (1994)
States that funds may not be made available to UNFPA unless:
– UNFPA keeps the U.S. contribution to the agency in a separate account, not to be commingled with other funds, and
– UNFPA does not fund abortions (note: language used beginning in FY00).
It also prohibits UNFPA from using any funds from the U.S. contribution in their programming in China.
UNFPA Funding; AbortionFunds made available to UNFPAYes, in effect.
Included in annual State-Foreign Ops.
UNFPA Dollar-for-Dollar Withholding of Amount UNFPA Plans to Spend in China During Fiscal Year (1994)
Reduces the U.S. contribution to UNFPA by one dollar for every dollar that UNFPA spends on its programming in China.
UNFPA FundingFunds made available to UNFPAYes, in effect.
Typically included in annual State-Foreign Ops.
Tiahrt Amendment (1998)
Prohibits the use of targets/quotas and financial incentives3 in family planning projects and requires projects to provide comprehensible information on family planning methods. Protects people who choose not to use family planning from being denied rights or benefits and requires experimental family planning methods be provided only in the context of a scientific study. Intended to “promote voluntarism and prevent coercion in family planning programs,” it specifically prohibits three types of targets: total number of births, number of family planning acceptors, and acceptors of a particular method of family planning.4
Voluntarism/
Informed Choice & Consent; Incentives and Disincentives
All FP funds under State-Foreign Ops.
 
Yes, in effect.
Included in annual State-Foreign Ops.
Reallocation of Funds Not Made Available to UNFPA (2004)
Provides for funds not made available to UNFPA to be reallocated to USAID’s family planning, maternal, and reproductive health activities/services (and, in some years, assistance to vulnerable children and victims of trafficking in persons).5
UNFPA FundingFunds appropriated for UNFPAYes, in effect.
Typically included in annual State-Foreign Ops.
Medically Accurate Information on Condoms (2005)
Ensures that information provided by U.S.-supported programs about the use of condoms is medically accurate information and includes the public health benefits and failure rates of such use.
CondomsAll funds under State-Foreign Ops.
 
Yes, in effect.
Typically included in annual State-Foreign Ops.
POLICY
USAID Policy Paper on Population Assistance (1982)
Outlines the longstanding USAID guidelines surrounding its fundamental programmatic principles of voluntarism and informed choice and consent.6
Voluntarism/
Informed Choice & Consent
All FP/RH assistance provided by USAIDNo longer in effect due to USAID’s dissolution.
Policy Determination 3 (PD-3): USAID Policy Guidelines on Voluntary Sterilization (1982)
Describes guidelines for informed consent and voluntarism specifically for voluntary sterilization services, including provisions to ensure ready access to other contraceptive methods and prohibiting incentive payments that might induce a person to select voluntary sterilization over another method.
Voluntarism/
Informed Choice & Consent; Voluntary Sterilization
All FP/RH assistance provided by USAIDNo longer in effect due to USAID’s dissolution.
Mexico City Policy (“Global Gag Rule”, 1984)7
As a condition for receiving U.S. family planning assistance, other global health assistance, and, now, also other U.S. foreign assistance (see “Applies to”), requires foreign NGOs and, now, U.S. NGOs, international organizations, foreign governments, and parastatals to certify that they will not provide or promote abortion as a method of family planning using funds from any source.
 
The latest iteration of the policy under the second Trump administration iss called “Protecting Life in Foreign Assistance” and falls under the broader umbrella of the “Protecting Human Flourishing in Foreign Assistance Policy” (PHFFA Policy), which also requires certain organizations to certify they will not provide or promote “gender ideology” and “discriminatory equity ideology,” among other activities.. Included in the U.S. Department of State Standard Terms and Conditions (see entry below), when applicable.
 
 
Abortion1984- 2003: when in effect, was applied to FP assistance at USAID only. In 2003, expanded to include all FP assistance at USAID and the State Dept., exempting multilateral organizations and HIV/AIDS funding under PEPFAR. 2009-17: Not in effect.
2017-2021: applied to all global health assistance.
2021-2025t: Not in effect.
2025-present: applied to most foreign assistance at the State Department.
Yes, in effect.8
USAID Post-Abortion Care Policy (2001)
Clarifies that post-abortion care – the treatment of injuries or illnesses caused by legal or illegal abortion – is permitted under the Helms Amendment and that any restrictions under the Mexico City Policy, when in force, do not limit organizations from treating injuries or illnesses caused by legal or illegal abortions (i.e., providing post-abortion care). Notes USAID does not finance manual vacuum aspiration equipment purchase/distribution for any purpose.
Post-Abortion CareAll FP/RH assistance provided by USAIDNo longer in effect due to USAID’s dissolution; however, the current Mexico City Policy does not restrict post-abortion care.
Guidance on the Definition and Use of the Global Health Programs Account: Section on Allowable Uses of Funds for Family Planning/Reproductive Health (2014)
Outlines allowable uses of funds for FP/RH by providing a description of activities allowed and examples of activities not allowed, addressing not only FP/RH activities but also family planning activities’ integration with other global health and multisectoral activities.
FP/RH Activities; FP/RH System Strengthening Activities; Integrated FP ActivitiesAll FP/RH assistance provided by USAIDNo longer in effect due to USAID’s dissolution.
USAID Standard Provisions for Nongovernmental Organizations (U.S. and Non-U.S.)
Outline requirements that must be attached to assistance agreements, including language implementing FP/RH legal and policy requirements described above (e.g., the Helms and Leahy Amendments.)9
 
Voluntarism/
Informed Choice & Consent; Incentives; Abortion; Involuntary Sterilization; Condoms; FP/RH Activities
USAID assistance agreementsYes, in effect in ongoing USAID award agreements with NGOs.
U.S. Department of State Standard Terms and Conditions (revised 10/01/2025)
Outline requirements that must be attached to assistance agreements, including language implementing FP/RH legal and policy requirements described above (e.g., the Helms and Siljander Amendments.)10
 
Includes the Promoting Human Flourishing in Foreign Assistance Policy (PHFFA Policy) – in effect as of Feb. 26, 2026 – for foreign NGOs, U.S. NGOs, international organizations, and, when applicable, foreign governments and parastatals.
Voluntarism/
Informed Choice & Consent; Incentives; Abortion; Involuntary Sterilization; FP/RH Activities
State Department assistance agreementsYes, in effect.
  1. As noted in CRS, Abortion and Family Planning-Related Provisions in U.S. Foreign Assistance Legislation and Policy, July 2022: “No restrictions exist on funding for the medical evacuation of Peace Corps volunteers who decide to have an abortion. Under existing policy, the Peace Corps covers the cost of evacuation to a location where ‘medically adequate facilities’ for obtaining an abortion are available and where abortions are legally permissible.” ↩︎
  2. In most recent years, a provision is included requiring that any Kemp-Kasten determination that is made must be accompanied by the evidence and criteria used to make the determination. ↩︎
  3. USAID defines a target/quota as “a predetermined figure that a service provider or referral agent is assigned or required to affect or achieve” for the purposes of the Tiahrt Amendment. It states that “the key to interpreting ‘incentives’ is to see whether they are provided in exchange for accepting a method (in the case of a client) or linked to achievement of a predetermined target or quota (in the case of program personnel).” USAID Global Health eLearning Center, “FP Legislative & Policy Requirements (Updated),” online course, February 2009, authored by Debbie Gueye, MSI. ↩︎
  4. USAID Global Health eLearning Center, “FP Legislative & Policy Requirements (Updated),” online course, Feb. 2009, authored by Debbie Gueye, MSI. ↩︎
  5. Although such reallocation began in practice in FY 2002, it was first authorized by Congress in legislation beginning in FY 2004 with reference to FY 2002 and FY 2003 funds. ↩︎
  6. Informed Choice: Effective access to information on family planning choices and to the counseling, services, and supplies needed to help individuals choose to obtain or decline services; to seek, obtain, and follow up on a referral; or simply to consider the matter further. Voluntarism: Decision to use a specific method of family planning or to use any method of family planning is based upon the exercise of free choice and is not obtained by any special inducements or any element of force, fraud, deceit, duress or other forms of coercion or misrepresentation. USAID Global Health eLearning Center, “FP Legislative & Policy Requirements (Updated),” online course, Feb. 2009, authored by Debbie Gueye, MSI. ↩︎
  7. This policy was first instituted via presidential memorandum in 1984 by President Reagan. In 1993, it was rescinded by President Clinton, although it was briefly applied legislatively in 1999 (see “Status” column). In 2001, it was reinstated by President Bush, who expanded its applicability in 2003 to include family planning funds at the State Department (see “Applies to” column) with some exemptions. In 2009, it was rescinded by President Obama. In 2017, it was reinstated by President Trump, who expanded its applicability to include the vast majority of global health assistance furnished by all departments and agencies. In 2021, it was rescinded by President Biden. ↩︎
  8. Note that, with one exception, has been applied via Executive action. The exception was in FY 2000, when President Clinton agreed to a one-year legislative codification with a partial waiver of restrictions as part of a broader arrangement to pay the U.S. debt to the United Nations. See P.L. 106-113, Sec. 599D, and PAI, Global Gag Rule Timeline, July 12, 2011. ↩︎
  9. “M16. VOLUNTARY POPULATION PLANNING ACTIVITIES – MANDATORY REQUIREMENTS (MAY 2006) …
    b. Prohibition on Abortion-Related Activities:
    (1) No funds made available under this award will be used to finance, support, or be attributed to the following activities: (i) procurement or distribution of equipment intended to be used for the purpose of inducing abortions as a method of family planning; (ii) special fees or incentives to any person to coerce or motivate them to have abortions; (iii) payments to persons to perform abortions or to solicit persons to undergo abortions; (iv) information, education, training, or communication programs that seek to promote abortion as a method of family planning; and (v) lobbying for or against abortion. The term “motivate,” as it relates to family planning assistance, must not be construed to prohibit the provision, consistent with local law, of information or counseling about all pregnancy options.
    (2)No funds made available under this award will be used to pay for any biomedical research which relates, in whole or in part, to methods of, or the performance of, abortions or involuntary sterilizations as a means of family planning. Epidemiologic or descriptive research to assess the incidence, extent, or consequences of abortions is not precluded.” ↩︎
  10. For example, one provision related to abortion included in the State Department Standard Terms and Conditions is:
    “AA. Prohibition on use of funds for performance or research respecting abortions or involuntary sterilization
    The recipient agrees that in accordance with 22 USC 2151b(f) Population planning and health programs no foreign assistance funds provided by the award shall be used to:
    (1) pay for the performance of abortions as a method of family planning or to motivate or coerce any person to practice abortions (Helms Amendment, 1973).
    (2) pay for the performance of involuntary sterilizations as a method of family planning or to coerce or provide any financial incentive to any person to undergo sterilizations (Involuntary Sterilization Amendment, 1978).
    (3) pay for any biomedical research which relates, in whole or in part, to methods of, or the performance of, abortions or involuntary sterilization as a means of family planning (Biden Amendment, 1981).
    Furthermore, the recipient agrees in accordance with the Department’s annual appropriation bill, that no funds provided by the award may be used to lobby for or against abortion (Siljander Amendment, 1981).” ↩︎

The Business of Health with Chip Kahn

Is AI Better for Patients?

June 2, 2026

Video

Audio

About this Episode


Episode 6, AI Series: Is AI Better for patients? What is changing on the ground? Chip talks with Dr. Patrick Conway, Chief Executive Officer of Optum, a health services and technology business under parent company, UnitedHealth Group. They discuss how to ensure the health care industry’s use of AI serves patients first, particularly when the same company bears financial risk and builds the AI that decides who gets care. They also discuss whether use of AI can make value-based care the dominant payment framework, after two decades of policymaker support for the model.

The Host


Headshot photo of Chip Kahn wearing a navy blue suit with a red tie, red pendant on lapel, and glasses.

Sr. Visiting Fellow

Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.

Guest


Chief Executive Officer of Optum

Dr. Patrick Conway is the Chief Executive Officer of Optum. He served previously as CEOs of Optum Health, Optum RX, and Care Solutions at Optum. Before joining Optum, Dr. Conway was president and chief executive officer of Blue Cross and Blue Shield of North Carolina. He also previously served as Deputy Administrator for Innovation and Quality at the Centers for Medicare and Medicaid Services and as director of the Center for Medicare and Medicaid Innovation and the agency’s Chief Medical Officer. Before joining CMS, he oversaw clinical operations and quality improvement at Cincinnati Children’s Hospital Medical Center.

Transcript


AI Usage Disclosure: This transcript was created with assistance from AI tools. It was reviewed and edited by KFF Staff.

Chip Kahn: Now we move from the health system actually deploying AI inside its hospitals to the health care company doing it across the full stack. One organization bearing the financial risk for care, delivering that care, building the AI that informs coverage decisions, and running the analytics that tie it all together. My guest today is Dr. Patrick Conway, CEO of Optum. No one else in American health care has occupied all four of Patrick’s positions. Regulator at CMS; payer at Blue Cross, North Carolina; pharmacy benefit operator at Optum Rx; and now the head of Optum itself. He designed the value-based payment models. Now he runs the platform meant to deliver them at scale. UnitedHealth is spending at least $1.5 billion on AI. But Patrick will walk us through what is changing on the ground: prior authorizations cleared in seconds; claims are adjudicated while the patient is still in the exam room; and, a true outcomes orientation. At the heart of this conversation, two questions sit alongside the proof points. First, when the same company bears financial risk and builds the AI that decides who gets care, how do you ensure the technology serves the patient first? And second, after two decades of policymaker support for value-based care, particularly in Medicare, can integration and AI finally make it the dominant payment framework? Below all of this sits the test each episode in this series returns to: is the patient better off? Not in the aggregate, but when receiving care in the examination room or the hospital bed. Let’s get started. Patrick Conway, welcome to KFF’s The Business of Health with Chip Kahn.

Patrick Conway: It’s great to be here, Chip.

Chip Kahn: This is great. Such a pleasure. We’ve worked together over the years and known each other for a long, long time and it’s just great to have you here. Before we get into AI and healthcare, although I think this question may touch on that, you were one of the key people that is responsible for designing value-based care and value-based payment models at CMS. Later, you ran the North Carolina Blue Cross plan and now you run the largest integrated health services company within the largest private health insurer in the world. What have you seen from the inside at Optum that you could not see from your earlier vantage points?

Patrick Conway: So, a few thoughts, Chip, and appreciate you having me in the discussion. At a high level, and then I’ll come back to the different stages. You need predictability, you need incentives aligned with total cost of care, quality and experience. And you need the ability to innovate and drive care at the front line on behalf of patients. So then let me take you through the stages that you alluded to and reflect on them. I started in CMS, I was in government twice, the second time through 2011, and then ran the CMS Innovation Center after serving as Chief Medical Officer. As you remember, we had almost zero percent of payments in value-based care models tied to total cost of care quality experience. At that time, you’re launching the ACO program, you’re launching these new CMMI models. The question was, would people participate? Participation went up, we got to over 30% participation by the end of 2016, ahead of schedule. It was a target President Obama had set. Then you’ve seen phases in the public sector, okay, now let’s move to two-sided risk. Now let’s do mandatory models when necessary. Now let’s figure out what’s working and expand those models, and you know, iterate on models. So that’s sort of the public sector side. You know, as I moved into the private sector, at Blue Cross, North Carolina, we actually went from almost 0% of payments in those kinds of models to 70 plus percent in about 18 months. And it was built on some of the lessons—I didn’t plan this out—but from the Innovation Center of partnering, of sharing data, of predictability, of saying, you know, fee for service is not what we want to do. We want to move to this value-based care model that’s integrated. And then at Optum, as you allude to, I’m sure we’ll talk more about this, you know, we have the ability of having the people, resources, and technology to deliver value-based care at scale. So, we serve millions of people across the country. Hospitalizations go down, most models in the high teens, less hospitalizations, unplanned ER visits go down, total cost of care improves significantly, quality 4-star plus in the vast majority of models and NPS or patient experience usually in the 80s to 90s so very high in these models. And I know you like data and stories I’ll share. You know, you see a 91-year-old in her home—this is a visit I went on—used to be hospitalized the year before, 10 plus times. Now has a primary care doc, a nurse care team, people have helped her with food delivery, helped modify her home, addressing her physical, mental, social, and financial needs. Now been hospitalized 0 times and hugs the doctor when she walks in the door. Not me, I am a doctor, but it was a real doctor with me, from our team. And that’s what it’s about, right? That’s better care for patients. So, when we get it right, it delivers exactly what we want for our own loved ones in the health system.

Chip Kahn: So, I think you just described the secret sauce. But how do you scale that, and how does this kind of pay-for-performance, value-based care become the prominent dominant payment scheme?

Patrick Conway: It’s interesting, this week I was in D.C. and the West coast so saw much of the country, and Massachusetts. Dr. Oz talked about this on a panel about, you know, he wants value-based care to be the model in the U.S. He wants 100% of patients and people in accountable care relationships. By the way, this is a bipartisan idea. It’s been across administrations. The good news is I think we’re getting much closer. So, you have over 50% of patients nationally in these models. It’s heading towards 50% and sort of two-sided risk models. So, I think we’re moving. You know then I think how do you get there? It’s going to be public private collaboration. It’s going to be continuing getting the incentives and the various payment incentives right. But that’s not all you need. You also need the technology, the clinical practices, the workforce, which you know is often organizations of a certain scale and capability to deliver those services. We may talk about rural today. That’s something we think about a lot now. How do we scale these models to rural settings as well so that we at Optum are serving the whole population. And you know, it’s not going to be one organization including Optum. It’s going to be a set of public private sector actors that are all moving in the same direction.

Chip Kahn: I have a feeling technology is going to be part of this. So, let’s now go to AI and UnitedHealth Group is spending a great deal on AI. You’ve got hundreds and hundreds of use cases that I understand you’re focused on and trying to operationalize. How is that investment going and what is the evidence that it will be transformative? How are you going to make it transformative?

Patrick Conway: Look, we think AI is going to completely transform our business. You know we talk about if we don’t transform and disrupt ourselves, somebody else will. So then let me describe; we’re now scaling use cases. So, I think we’re at the sort of next phase of the journey. I’ll put them in categories. You’ve got what I’ll call administrative type functions. So, think, call, claim other things. How do you make the system work better? We take about 300 million calls in UnitedHealth Group. We think that could be 150 million or less in the next 12 to 18 months. So many of these investments we think will get an in-year return and then a long-term return. Let’s go to another area. Products and services. So, Optum Real, which is real time settlement of claims. The payer agrees what they’re going to pay, based on what we’ve digitized and used AI on, the benefits, the provider, we’ve pulled the clinical data and made sure we’ve met all the criteria. I think 99 plus percent approval at the point of care. And the patient knows what their copay is and can settle that right away. It’s how the system should work. So, we’re scaling that across payers and providers. You know, also things like ambient listening combined with AI technology. So, the clinician could just practice and then it’ll automatically or autonomously code for them so they’re not spending as much time with documentation. One of the stats I loved: some of this work has saved over 2 million minutes of clinician documentation time just in our system. So let them get back to patient care. I know, you know, I’m still a practical physician. I use the EHR on weekends in the hospital. and you want to focus on the patients, right? Last clinical, I just, I know I’ll try not to be too long winded, but the clinical example, I’ll give that I think we’re in the early stages of. My first week as an attending. I finished residency at Boston Children’s. I go to Children’s Hospital Philadelphia. I get a patient who had been referred all around America, people trying to figure out the diagnosis, about a thousand-page chart. I get to page 487 and I’m like, oh my gosh, this kid has a rare metabolic disorder. Which ended up being the case. That took hours of reading. In an era of AI, that should be queued up to me or any other clinician anywhere in the country. You know, the nurse practitioner in rural America. So instead of two years, that child’s diagnosis may be done in minutes. That’s the kind of potential impact the technology could have.

Chip Kahn: On the paperwork side, in a sense, the sort of rift between providers and payers. What can it do with prior authorization? I know that you’re applying it there and you’re trying to cut back on the number of times that prior auth is required. What do you see the developments there that are going to bridge some of these gaps we have right now?

Patrick Conway: First, as you alluded to, we are both across UnitedHealthcare and Optum, eliminating prior authorization whenever possible. So, decreasing the prior authorization  burden, if you will. And then we’re standardizing and using electronic tools. So let me give you a couple examples. At Optum Rx, our pharmacy business, we once again connected all those benefits using the pharmacy rails into providers. The median prior authorization team had been eight hours, sometimes days or weeks for medicine, we got it down to less than 30 seconds. So, it’s auto approved, by the way, if the clinician, the prescriber, you need one more piece of information, which is usually why prior authorization gets caught up because you don’t have all the documentation. It tells them right then so they can enter the information and get it approved. So that’s how a system should work. We’re also doing that for medical as well through Optum Insight. So, you get approval rates that are very high immediately and they’re in the clinical workflow, which you know, that was prior auth’s original intent, right? Get the right treatment to the right patient. That we can all stand behind. But we have to have a system that makes it fast, standardized, and seamless for the patient and the clinician.

Chip Kahn: In terms of your 91-year-old patient example, how broad based is that in terms of having that integrated platform, at least in your system right now? I mean, are most of the patients getting that total coordination integration or is it just being experimented with? Where are you with that?

Patrick Conway: Yeah, so in our Optum Health platform, integrated value-based care, we serve about 20 million patients today. It’s, by the way, across about 100 payers. It’s national, so it’s large scope. You know, as you alluded to, there’s obviously more Americans in our health care system so there’s more room for growth or expanding the model. But our integrated value-based care platform is impacting millions and millions of people all across the country. And to be clear, Medicare Advantage and duals are the most in that platform. But we also serve Medicaid and commercial on the platform. It’s across all lines of business. As I said, sometimes people forget sometimes we actually serve about 100 payers. So, it’s UnitedHealthcare and all the big nationals, but also regional blues and other health plans as well.

Chip Kahn: Are you using data to locate those patients? What kind of systems do you have?

Patrick Conway: We’re an evolution, transformation, whatever verb you want to use as well. So, we do, and I think those are getting better over time. So, let me try to give you an example. In our various clinics and specialties, we’re trying to make sure we match demand, so patient demand for appointments and things like that to supply. So, we get people to the right clinician quick enough. Actually, mental and behavioral we haven’t talked about yet today, very important. We have about 4,000 mental and behavioral health clinicians. So, psychiatrists, therapists and others. Obviously huge demand. We use technology to try to match that demand to the supply and including through virtual care, also in person, but a large percentage virtual. The last thing I’ll say on sort of clinical pathways in our Optum Insight, Optum Real business, and Optum Health. As we think about guiding patients, we’re increasingly saying, you’ve got a patient with a clinical need. How do we navigate them to the right place? That could be an Optum clinician, that could be a hospital, that could be wherever the right place is. So how to use data and technology and partnerships to sort of find that clinical need earlier and then guide them to the best clinical pathway for them.

Chip Kahn: You know, you’re big. In a sense, there are a lot of people within the whole umbrella, where it’s the same company bearing the risk for the care that bills the AI that informs the coverage decisions. How do you ensure that AI serves the patient first and is seamless for the provider? And what does your sort of AI review board or however you process things, actually do to give confidence to the answer?

Patrick Conway: We do have an AI review board that reviews the technology and its principle is sort of patient quality safety first. Since I’ve been at Optum, I’m in my seventh year now in all the various businesses, and I’ve run different businesses over time, now I just started my second year as CEO of Optum. We always start with a patient story. So, you center on the patient, the clinical first. So, we actually did it yesterday, our monthly business review. It was a child with multiple chronic conditions that we care for in the home. And we care for her almost every day of her life because we have a big home health hospice business as well. You know, that’s why you do the work. Then as you do, you take that principle into AI and you’re always clinical first. As I said, we’re using it for clinical approvals, automatically. You know, if it’s changing direction of care or saying we don’t think the therapy is needed. We have a principle that a clinician must review that—a human doctor, nurse practitioner, or other—the appropriate clinician. Because where we are now on the paradigm, we think that’s important that a clinician has the final say on approvals, auto approval by the technology for anything that is a redirection of care. We think that final decision, aided by AI and technology, but should be made by a clinician.

Chip Kahn: With that principle though, and not focusing on one, United or other companies. There is litigation, legislative activity in this whole area around AI-driven coverage decisions. How do you engage? And in some ways, you just did it. But public concern about AI being used to limit access. How do you assure people? And maybe also what kind of guardrails or public policy do you think are appropriate here?

Patrick Conway: Yeah, so first on us, I’d go back to the principles. I said, so what’s the review of the technology overall for patient quality first? And then I think principles like I described, auto approval, making the system faster, the technology can enable that. Redirection of care, or saying that, you know, this treatment is not approved, we think a clinician, you know, typically a doctor, has the final say. Then how do we assure people? I think it’s around transparency. I don’t know if we’re going to talk about Optum Rx today, but I’ll just—we put out the culmination of a series of work on Monday that is 100% transparency, 100% rebate pass through, 100% transparency down to the group purchasing organization, cost-based reimbursement for all drugs, 100% of independent pharmacies. They actually—Buddy Carter, who, you know, did a positive tweet about Optim Rx that’s, you know, you don’t see that every day.

Chip Kahn: Right.

Patrick Conway: I think it’s the same in AI. If we provide transparency, that builds trust. And so, one of our principles is providing that transparency to build trust. Sorry, last thing I’ll say here, because you alluded to a couple different ways. The health care system has many broken, fragmented parts. You actually need scale, whether you’re a UnitedHealth Group or a health system or public private partnerships to address people’s physical, mental, pharmacy, social needs at scale. I’d almost flip this question on its head sometimes. Individual niche solutions may solve individual niche problems. But if you want to make health care better for millions and millions of people, you actually need the capabilities, the assets, the people, the technology to do that. And that often comes with scale to deliver those outcomes.

Chip Kahn: Yeah, I think what you just articulated is really important and there are a lot of naysayers about…I’ll use the consolidation word. But at the end of the day, if you can’t do most of what the patient needs in some kind of system, then the patient’s not going to get what they need. Fragmentation is a problem. I mean, there’s no question about it.

Patrick Conway: Totally. Look, to bring it to the clinical: I was down at Kelsey-Seybold [Clinic] a while back, which is one of our clinics systems in Houston and they have a product that actually the network is more open than you might imagine. I said, well, how do you keep people coming to Kelsey-Seybold? And they’re like, well, they love us and we do everything. We got primary care, we got specialty care, we got ambulatory surgical centers, we got mental health. And to your point, you need the scale and set of capabilities to do that. And actually, the data proves it out. They’re lower cost by far. Their quality results are through-the-chart positive, and their experience results are very positive. I mean, sometimes you can’t make this up. I’m not going to name the person because I don’t know if you want me to, but I met with senior officials in Massachusetts yesterday and he had been to one of our ambulatory surgical centers. And you’re a little nervous when that happens because you’re like, oh, he was like, he was like, no, it was amazing. Like, it was the best health care experience I’ve ever had. It was patient centered, it was organized. You guys had transferred my primary care record to the ASC [ambulatory surgery center]. I mean, that’s what you want for patients and that is the benefit of some level of scale capabilities, technology to support that level of care.

Chip Kahn: So, let’s move from the patient side to the physician side. You know, there’s some data out there that maybe you can even give us the number of the total physicians that you employ. But Optum docs, I understand, run 34% below industry average in terms of burnout, which is, which is a really incredibly positive number. What is different about a doctor’s day inside your model? And how are you keeping them in the race and not burn out?

Patrick Conway: You do your research. I’m impressed. You know that stat, that is the right stat. We basically try to support them in the clinical care and remove the barriers. And then let me describe. We use ambient listening powered by AI to help them with documentation. We use AI and technology to queue up, have you thought about these clinical decisions? Have you thought about these Star gap closures? So, it’s helping them manage. I mean, you know, I still practice. You’re managing a kid or an adult with 10 plus chronic conditions and many medications. It is a recipe for, on one end of the spectrum, errors or safety errors. On the other end of the spectrum, you know, making sure you address every care gap and address all their needs. We’re supporting them with the latter. Give you some other tangible examples. I live in Massachusetts. I interact with our Atrius physicians a fair bit. They were struggling as an independent. Now they’re expanding, they’re expanding services. They have the technology to do what they need to do. They’ve got home health and hospice and the whole care paradigm, ambulatory surgical centers to serve patients. The last story I’ll tell: It’s actually the flip with a 91-year-old story with one of our geriatricians who do those visits often. She said to me, you know, I was going to retire. She was older in her career and she said, and then I found this and I love it. She was like, I was doing 15-minute office visits, burnt out, could never do everything I wanted. And now I get to drive around and see four or five people in their home and do a visit for an hour, hour and a half. She’s like, this is amazing. Like I love it and I don’t plan to retire anytime soon. So, I mean that you give physicians the ability to practice or nurse practitioners or other clinicians and just deliver amazing clinical care. That’s why they went into medicine, that’s why I went into medicine. And you do the opposite and you create barriers or paperwork or other things, then you end up burning people out. So, we’re trying to do the former.

Chip Kahn: So how much is AI, contributing on this clinical side to diagnostics and are we headed to automated decision-making in this at all? And where’s the accountability? I know you talked a bit about it, but could you put more emphasis on it?

Patrick Conway: Yeah, I think AI is going to be a huge accelerator. So, there’s even a study came out I think, yesterday or the day before, on sort of physicians using AI and various tools. And it’s a very high percentage now what they’re generally, I use it by the way in my clinical practice as well, it’s used as an aid, a support system. And I think that in today’s paradigm that’s the way it should be used. So, if it’s diagnosis, what are the various diagnosis to consider? I like data and stories as you’ve heard. Our care at home model, we broke patients into various cohorts. So, you’ve got a 40-year-old disabled patient versus a 92-year-old patient versus an oncology patient. So, you’re queuing up the right information based on AI technology for that specific patient. It also becomes much more personalized. As you know, patients are starting to use AI to help guide their journey. I think that’s good. It’s giving them information and clinicians are using AI. So, I think it becomes much more personalized, if you will, to get the exact right care for that individual patient in front of you.

Chip Kahn: You’ve committed to pretty significant cost reductions from AI in ‘26 and argued that capitation and generative AI together can bring about value-based care. And this is where we get into the rural side, to rural communities. If you were right and obviously if you’re saving money, some of that’s sort of coming out of the payments and the volume. What happens to the independent physician, that local community hospital, and the smaller players in that market?

Patrick Conway: A couple things. I grew up in Texas, I certainly understand rural health care. With a doc that, you don’t do this anymore, did one year internship, hung a shingle, delivered us, did minor surgery, my entire medical records, like five pages. You don’t see that much anymore, handwritten. We need to support these hospitals and clinicians. Then let me describe that. So, we actually serve a little north of 8 out of 10 hospitals and health systems in the country in some way, usually in a lot of their back-office functions. A ton of those are in rural America. We’re committed to that; we’re committed to doing more of it. We even through our UnitedHealth Group foundation are talking about how we invest even more in rural, both as a business and a foundation. For those independent docs, as you alluded to, we often are given a physician number and people include contracted employed. Employed is actually a smaller percentage of the number. The vast majority are contracted, which means they’re not employed by us. We’re offering them tools, technology, and contractual arrangements to allow them to participate in value-based care. As you know, as a small doc practice, that’s very hard on your own. And many of those are in rural areas and we want to expand those and even more in rural areas. So, the rural hospitals, we support many of them now and we’re having these kinds of conversations. How do we use AI and technology to help you be more efficient, help you get the right patients in your door. Also, you know, when patients need to transfer, go somewhere else. How do we make that process as simple and fast and efficient as possible?

Chip Kahn: Can we go into a little bit more depth, and maybe beyond what you’re doing in terms of rural health care? We have in the OBBA [One Big Beautiful Bill Act ] very large Medicaid reductions and frankly from at least my perspective, we have a small little rural program. And the administration’s made it clear they don’t want to use that money for helping directly to providers. So, there’s going to be a gap and it’s not going to come all at once. It’s going to be over the next few years. But that gap is going to be really significant in terms of those rural hospitals that are very dependent on Medicaid and Medicare. And the Medicaid numbers that they’re paid is going to come down. Do you have a view as to how that should be dealt with? How we can mitigate that at all or…?

Patrick Conway: Look, it’s a major issue. My hypothesis is we’re going to need public and private sector to sort of fill in because gaps, if you will, and partner in rural America. We’ve talked to the current administration about this. You know, rural health has actually generally been bipartisan over time. Certainly something we care deeply about. Look, I think you’re going to have to fill in with technology data supports. I think payment models you’re going to have to think of slightly differently. So, give you an example. You know, in the Innovation Center, we had this rural hospital model in Pennsylvania that basically tried to support them if they wanted to become a smaller sort of inpatient surgical footprint and more of an ER and a community footprint, they could do that and gave them the glide path. In Vermont, we did this all-payer ACO model which also tried to support the rural hospitals. So, I’d look to some of the state-based work as well, not just those two generally that have said, you know, we need a system of care in this state that includes rural and urban and how do we make that system function as best as possible?

Chip Kahn: I mean, something’s got to be done. It’s not going to get better by itself.

Patrick Conway: Exactly. And you know, we read about the alternative, right, where you now have a desert where, you know, I have to drive two and a half hours to deliver my child. You know, to deliver a baby. That’s obviously not optimal. You know, there in a given state, I’d literally map that out to figure out, you know, where do I have those kinds of significant access concerns? How do I as a state support something in that area, even if it’s a smaller physical footprint, not a whole hospital, but some ability to do the more emergent and basic care? And I’d include childbirth, it’s a specialty, but it’s an important specialty that is incredibly important at the time you’re delivering a child. So how do you have that spread out with access uniformly, including to rural areas.

Chip Kahn: You brought up the Rx and you talked about the refinements that you all were making in your pharmacy benefit management function. What role will AI play on the pharmacy side? I know in Utah they’re back and forth about an experiment of having scripts refilled using AI. What’s your view on that?

Patrick Conway: Yeah, so I’d put in categories again. So one, we are using AI for auto approval, like I said now, the median is less than 30 seconds. So, I mean, you know, we literally had a very senior person in our company. It was like, it worked on my phone, like it was ordered and approved, you know, all done. And that’s how it’s supposed to work and that is how it works. So median less than 30 seconds for auto approval. The other place we’re using AI, this cost-based reimbursement for all drugs, all pharmacies across America. One of the challenges before was the data to try to get there. So how do you sort of, you know, you got thousands and thousands of drugs, thousands of pharmacies. So, we actually had an AI technology pricing platform it was part of the solution to allow us to move to a cost-plus type of arrangement for all drugs, all pharmacies. And the feedback we’ve gotten from independent community pharmacists is very positive. Actually, a rural issue as well. You know, if you’re a rural independent community pharmacy, we can support you in a sustainable cost-plus model. We won’t have a pharmacy desert in that area, as an example. The last area I’ll put in is a large part of our Rx business is also the pharmacies. So, think infusion, specialty pharmacy, home delivery. We actually have these community pharmacies that are integrated care for mental and behavioral. So, think schizophrenia, substance use disorder, really cool model, partner with FQHCs and community health centers. The data there is similar to some of the clinical realms. You know, how do we get the nurse to the right patient? How do we make sure this, you know, right drug, right patient, right time, affordably, right dose, you know, how do we make sure that happens every time using AI and technology. So those are some of the ways we’re using it in the Rx space.

Chip Kahn: One of the other issues that comes up, and there have been some Wall Street analysts on this, talking about whether AI in terms of the clinical area will save money or reduce spending immediately. And the issue is, I think, really characterized by one of our earlier interviews with Elad Walach from Aidoc, where their technology now is so good that even if they have a CT scan that was ordered for a certain purpose, they can find out a lot of other stuff about that patient. So, as we apply AI to whether it’s population health or whether it’s specific procedures or diagnostics, you’re going to be finding things you didn’t see before. So where do you fall out on this notion that at least at the beginning it’s going to find more disease, which will have to be dealt with before we get to the longer-run benefits of finding things earlier? You, know, where do you fall out on this?

Patrick Conway: Yeah, look, I go back to first principles. There will be instances where AI finds something earlier. I would argue that’s unequivocally a good thing if it improves health. You know, so if you’re improving health, that’s our first principle goal—health care outcomes and quality and experience. And over the long term, most of those things will have a cost, return as well. There was actually. I’m looking,  I got books above me. Somebody wrote in one of their books about this. You may remember this, when we did the diabetes prevention program in CMMI, I actually had to approve. The actuary said, well, it does improve in quality. It does. You know, it clearly saves lives. By the way, in our 10-year window that we use for everything in D.C., it may increase cost. And we actually said we still want to expand it nationally because the goal of Medicare should be to improve life and health outcomes. And, by the way, a 10-year window is pretty arbitrary, and so we approved it and expanded, as you know. Look, the reason I share a story is similar here. Anything we can do, or anybody in the health system can do to improve quality of life, health outcomes, morbidity, mortality, we should do, because that’s what our population that we serve wants. And the vast majority of those things do have a financial return over some time period. Some of them will be longer, some of them will be shorter. But we need to invest in health.

Chip Kahn: You know, one of the dilemmas in the whole area of pay-for-performance is that, you know, obviously it usually has a pricing angle, and it has some kind of volume angle, but it also includes some kind of metrics. But those metrics are usually structural or process.

Patrick Conway: We worked on this.

Chip Kahn: We did, and it was the best you could do at the time. But we’re sort of stuck with a system that at best, I could say, is not dynamic and may not even be relevant to the services that are being provided. It’s really about compliance now. Do you think that AI can—and obviously we have all the data—AI can break the logjam here.

Patrick Conway: I do. I was smiling because we did work on it and you’re right, we did the, you know, Medicare stars, which we put in when I was at CMS. It was the best for the time. It was. It needs to evolve faster to more outcome-oriented measures, to measures that actually matter. And you know, the current administration agrees with that by the way, as do we. So, I do actually think AI and technology may be the final breakthrough, if you will, because one of the biggest limits before, as you know, was the data. Well, I don’t have the outcomes data, I don’t have the clinical data. Oh, it’s too expensive to collect, you know, so we’re just going to rely on claims data because that’s what we have, you know, or a process metric that we happen to have. That was what you had at the time, but now you’re in an era with the AI technology that you should be able to have the data. It should not be costly to collect. You should actually know the health outcomes. And so, I do think it opens up the health outcome and quality measures to be much more meaningful and actually have that parsimonious set we’ve talked about for so long in the various areas that are the measures that matter.

Chip Kahn: You know, as we close out our conversation, Patrick, there are a lot of doomsayers about AI, generally, as well as those who look at it as making the future brighter. In terms of AI and health care sort of generally, is there anything that keeps you up at night that worries you about where we’re headed?

Patrick Conway: Look, what’s kept me up at night through various…actually, I fall asleep in about two seconds, but if anything kept me because I probably don’t get enough sleep, although I’m trying to get back. But if anything kept me up at night, I’ve had the blessing, if you will, to work at places like CMS and UnitedHealth Group and Optum that serve millions and millions of people. And then what would keep me up or worry me? There’s somebody falling through the cracks. And actually, when I work clinically in the hospital, I work at a safety net hospital in Boston. I see those people that fell through the cracks, didn’t get the mental health care they needed, didn’t get the home-based care they needed, didn’t get basic preventative care. So that’s what keeps me up or worries me. I’m an optimist. I actually think AI is one of the keys to solving that problem, because one of the challenges as a clinician, you don’t see the patient not in front. You see the patient in front of you. And we literally train clinicians that way. But in population health or value-based care, you have got to care for the whole population. To do that, you’re going to need AI and technology to help you see and understand that whole population and serve their physical, mental, pharmacy, social, financial needs across their life trajectory. And that I think AI and technology are the key to. And what gives me hope is when I’ll, go out and see this care. I’ve got to end with one story that I hope you keep in the podcast.

Chip Kahn: We’ll keep it. We’re going to keep it all though.

Patrick Conway: Yeah, it’s not AI, but it’s caring. So, I’m in Lafayette, Louisiana, and I like to do visits, so I show up at this house and the nurse walks from across the yard and I’m like, are you his neighbor? And she says, yeah, I’ve cared for him. You know, when I was a single mother, he helped me help repair my house, he helped do other things. I’m a hospice nurse. He was going into hospice. There was no question I was going to care for him. And we walk into the home and his caregiver, these are these nurses employed by us, the caregivers employed by us watch from the backyard. You can’t make this up. I care for him 50 hours a week because he’s my neighbor. You know, I work. LHC is the business. It’s one of our home health hospice businesses. And the emotion in that room was palpable. And then you walk out and the nurse says, do you have a minute for an elevator speech? Do you know what an elevator speech is? I’m like, of course I do. She gives a speech about hospice and about how it’s important to care for people at birth. It’s just as important at the end of life. And that she cares for their physical, mental, social, pharmacy, their whole holistic needs. That’s when you know you got it right. And we do support her with technology as well. To bring it back to your AI topic. But it’s not just technology, it’s the caring of a clinician like that and giving them the tools and the technology so they can do their best work.

Chip Kahn: Thanks, Patrick, for a great conversation. I really appreciate your time. And I certainly learned a lot today and I know our audience will appreciate it also.

Patrick Conway: Well, thank you. I’m a learner, too.

Chip Kahn: Great.


SERIES

This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.

The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.

A Closer Look at North Carolina’s Implementation of the 2025 Reconciliation Law Medicaid Provisions and Other Changes Amid Medicaid Budget Shortfalls

Published: May 29, 2026

On April 30, 2026, North Carolina Governor Josh Stein signed legislation that includes Medicaid policy changes and closes an estimated $319 million shortfall in funding for the state’s Medicaid program for FY 2026. Many of the legislation’s Medicaid policy changes are related to implementation of the 2025 federal reconciliation law. The 2025 reconciliation law requires states to condition Medicaid eligibility for adults in the Affordable Care Act (ACA) Medicaid expansion group and enrollees in partial expansion waiver programs (Georgia and Wisconsin) on meeting work requirements starting January 1, 2027. The 2025 reconciliation law also limits states’ ability to raise the state share of Medicaid spending through provider taxes, restricts state-directed payments (SDPs) to hospitals, nursing facilities, and other providers, and increases barriers to enrolling in and renewing Medicaid coverage. As states are preparing to implement the reconciliation law provisions, many states are facing more tenuous budget situations with slowing revenue growth and broader reductions in federal funding.

This policy watch examines the current budget context in North Carolina, the state’s recently passed legislation, the state’s Medicaid Advisory Committee (MAC) meetings, and data from KFF’s Medicaid work requirements tracker to provide initial insight into how North Carolina is preparing to implement certain Medicaid provisions of the 2025 reconciliation law and how other policy changes may affect coverage and access to care. While some of the issues North Carolina is facing are unique to that state, others are likely to be faced by other states as they implement federal changes to Medicaid in the midst of other fiscal challenges.

What is the budgetary context as North Carolina prepares to implement the 2025 reconciliation law’s provisions?

North Carolina is facing a more tenuous fiscal climate like in other states, and state legislators have not yet enacted a comprehensive state budget for the FY 2025-27 biennium. In the past year, revenue volatility and rising costs have led to slowing state revenue growth following a period of record-breaking revenue and expenditure growth for states after the initial pandemic-induced economic downturn. In North Carolina, scheduled tax cuts have been projected to drive declines in state revenue, and debates over whether to proceed with the cuts have contributed to a budget stalemate in the legislature.

In August 2025, Governor Stein signed a stopgap funding bill  that appropriated $600 million from the state general fund for Medicaid, but it left a $319 million shortfall for FY 2026 in funding for the cost of services for non-expansion (traditional) enrollees. The shortfall and budget stalemate led to rate cuts and the elimination of GLP-1 coverage, both of which were eventually restored. The Medicaid agency ceased “Healthy Opportunities Pilots” program services in FY 2026 due to a lack of appropriations. The pilots covered certain non-medical services that target social needs, including housing, nutrition, transportation, and interpersonal relationship supports to specific and limited enrollees, and evaluations of the “Healthy Opportunity Pilots” 1115 waiver showed lower costs over time and largely positive outcomes. The Medicaid agency also implemented changes to reduce administrative expenses, including reducing temporary staff and contractors, ending certain contracts, pausing quality improvement projects, and scaling back compliance and quality oversight activities. The legislation signed in April 2026 appropriated $319 million to close the shortfall for FY 2026 and made changes aimed at addressing financing pressures associated with new federal limits on provider taxes, which the state uses to help finance its Medicaid expansion and hospital state directed payment program (which increases payment rates for hospitals).

What are some of the Medicaid policy changes included in North Carolina’s recent legislation?

Eligibility and Cost Sharing

North Carolina’s new legislation includes more restrictive standards for how the state will implement work requirements than is required in current law. At a minimum, the 2025 reconciliation law requires states to look back one month immediately preceding the application month and one month between renewal periods to confirm compliance with the requirements. North Carolina’s legislation requires the state to confirm compliance for the three months preceding the application month. At renewal, the state must confirm compliance for at least three of the six months since the last determination of eligibility. The North Carolina legislation also prohibits the acceptance of self-attestation as the only evidence in verification of eligibility requirements (unless required by federal law or regulation, or pursuant to a court order). States await guidance from CMS as to whether self-attestation of medical frailty, parent/caretaker status, or other exemptions or work status can be accepted, but most states report plans to accept self-attestation if allowed. 

The legislation increases the frequency of data checks to identify changes in circumstances for Medicaid enrollees from quarterly to monthly. The state will review information on earned and unearned income, employment status and changes in employment, residency status, enrollment status for other public assistance programs administered by the state and outside of the state, financial resources, incarceration status, and lottery and gambling winnings. States are required to follow up on reported changes that potentially affect eligibility and give individuals an opportunity to respond before taking adverse action. In North Carolina, when data indicates an individual is no longer eligible, enrollees only have 10 days in advance of case closure to submit documentation verifying ongoing eligibility. Increasing the frequency of periodic data checks with insufficient response times can lead to procedural disenrollments and exacerbate churn.

The Medicaid agency will be required to set Medicaid copayments at the highest allowable amounts for both traditional Medicaid enrollees and ACA expansion enrollees. Current federal rules limit cost sharing in Medicaid because of enrollees’ low income and limited ability to pay out of pocket costs. The maximum allowable cost sharing varies by type of service and enrollee income. North Carolina has set current cost sharing amounts, regardless of enrollee income, at $4 per service. Starting July 1, 2027, the legislation requires the Medicaid agency to increase current cost sharing amounts for services where the maximum allowable amount is more than $4 and to increase cost sharing for ACA expansion adults with income 100-138% FPL to up to 10% of the cost of the service, except for prescription drugs and non-emergency use of the emergency department. Beginning in October 2028, when states are required to implement mandatory cost sharing of up to $35 per service for ACA expansion adults with income between 100%-138% FPL, the state will be required to set cost sharing amounts at $35 per service, except for prescription drugs, for all non-exempt services for this group. 

The legislative text implementing the changes to Medicaid eligibility for certain lawfully residing immigrants effectively ends the state’s long-standing optional Medicaid coverage for lawfully residing children and pregnant immigrants without a five-year waiting period. The law limits Medicaid coverage for immigrants to coverage that is required under federal law. However, North Carolina is one of 40 states that have taken up the option to extend Medicaid and/or CHIP coverage to children and/or pregnant adults who are lawfully residing and waive the five-year wait for these groups. The 2025 reconciliation law imposed additional eligibility restrictions for many lawfully present immigrants but allows states to maintain the option to cover lawfully residing children and pregnant adults. By limiting coverage for immigrants to only what is required by federal law, the state law effectively ends this optional coverage as of October 1, 2026. In a recent Medicaid Advisory Committee (MAC) meeting, the Medicaid agency indicated it was working with the legislature to make “corrections” and restore coverage for these populations.

The legislation requires the Medicaid agency to report certain Medicaid applicants and enrollees for whom it cannot verify citizenship or “satisfactory” immigration status to the Department of Homeland Security. These include applicants and enrollees who, after a reasonable opportunity period, have not verified satisfactory immigration status or whose final verification indicates that they do not have a satisfactory immigration status and are not lawfully present. This group would include those found ineligible based on immigration status and individuals receiving Emergency Medicaid services (where Medicaid pays hospitals for emergency care provided to ineligible immigrants who would otherwise be eligible for Medicaid based on their income).

Medicaid Financing

The legislation increases intergovernmental transfers (IGTs) from public hospitals, reducing reliance on the state’s hospital taxes for financing the nonfederal share of Medicaid spending. The 2025 reconciliation law imposes significant new restrictions on states’ ability to generate Medicaid provider tax revenue, including prohibiting all states from establishing new provider taxes or from increasing existing taxes, as well as reducing existing provider taxes for states that have adopted the ACA Medicaid expansion. North Carolina uses provider taxes to help finance the nonfederal share of Medicaid spending. State law requires the nonfederal share for the expansion program to be fully funded by certain non-general fund sources, including hospital taxes and hospital IGTs, and requires the end of expansion coverage if those sources cannot fully fund the nonfederal share. The state estimates $14.3 million in one-time administrative costs for the current state fiscal year and $44.4 million in recurring annual administrative costs (including both state and county expenditures) for the expansion program to implement work requirements and six-month eligibility redeterminations that existing financing mechanisms did not account for. The increased public hospital IGTs aim to offset the financing of some of the existing costs under the state’s hospital tax, as well as to help finance the new administrative costs.

By increasing reliance on IGTs as a financing source, the state may aim to retain higher hospital SDPs under new federal provider tax limits, but new federal requirements for state directed payments are expected to require further changes. North Carolina’s Healthcare Access and Stabilization Program (HASP), a hospital SDP program launched alongside Medicaid expansion in 2023, is also financed through hospital taxes and IGTs. An earlier state report indicated the new federal provider tax limits would eliminate all or most of HASP SDPs. The state has been using HASP payments to incentivize hospitals to relieve medical debt, and as of October 2025, more than $6.5 billion in debt had been relieved for more than 2.5 million North Carolinians under the initiative.

There is significant uncertainty about how federal regulations and state legislation may affect the state’s plan for financing the nonfederal share of Medicaid spending, including for the Medicaid expansion and HASP. New proposed rules on state directed payments and forthcoming provider taxes may affect the state’s financing plans. The state’s legislation created a “trigger” to end the new funding should HASP payments fall below certain thresholds or a change in federal law or regulation result in at least a 20% decrease to IGTs.

Medicare Advantage Out-of-Pocket Limits: Variation and Trends

The Average Medicare Advantage In-Network Limit is $5,421 in 2026, But Nearly 1 in 5 Enrollees Face In-Network Limits Higher Than $7,000

Published: May 28, 2026

For coverage of Medicare benefits, people face a choice between traditional Medicare and private Medicare Advantage plans. While there are many distinguishing features between these coverage types, one key benefit of Medicare Advantage is an annual cap on out-of-pocket costs for medical benefits, which traditional Medicare does not include. In 2026, the out-of-pocket limit for Medicare Advantage plans may not exceed $9,250 for in-network services and $13,900 for a combination of in-network and out-of-network services, but plans can have lower out-of-pocket limits than the maximum.

Policymakers have long considered whether to add a similar out-of-pocket cap in traditional Medicare. In 1988, Congress enacted a Medicare out-of-pocket cap, but the law was repealed one year later principally due to concerns about the financing mechanism. The Medicare Payment Advisory Commission (MedPAC) has recommended changes in traditional Medicare to give beneficiaries better protection against high out-of-pocket spending, including an out-of-pocket cap as part of a broader redesign that also includes combining Part A and Part B deductibles and simplifying cost sharing. Traditional Medicare remains the only major form of health insurance that does not include a cap on out-of-pocket spending, though most beneficiaries in traditional Medicare have additional financial protection through supplemental coverage, including Medicaid, employer- or union-sponsored retiree coverage, or a Medigap policy (which may require additional premiums).

This brief analyzes out-of-pocket limits in Medicare Advantage plans in 2026, variation by plan type, the distribution of enrollees facing different out-of-pocket limits, and trends over time. Of note, this analysis does not show the share of enrollees that reach their plan’s out-of-pocket limit in any year because spending data are not available. The analysis includes Medicare Advantage plans generally available for individual enrollment, reflecting coverage for 21.3 million Medicare beneficiaries in 2026, excluding special needs plans and employer-and union-sponsored group plans (See Methods for details).

Takeaways

  • In 2026, the average enrollment-weighted out-of-pocket limit for Medicare Advantage enrollees is $5,421 for in-network services and $9,825 for in-network and out-of-network services combined. The average out-of-pocket limit for in-network services is higher for preferred provider organizations (PPOs) ($6,592) than health maintenance organizations (HMOs) ($4,636).
  • Just over one in ten Medicare Advantage enrollees (13% or 2.8 million people) are in plans with limits of $3,000 or less for in-network services in 2026, more than two-thirds (68%) are in plans with limits above $3,000 and up to $7,000, and about one in five (19%) are in plans with limits above $7,000.
  • About one in 10 (9%; 1.8 million) Medicare Advantage enrollees are in plans with the maximum out-of-pocket limit for in-network services ($9,250). Among the 8.6 million enrollees in PPOs, roughly one in five (22%; 1.8 million) are in plans with the maximum out-of-pocket limit for in-and out-of-network services combined ($13,900).
  • The average out-of-pocket limit for in-network services decreased by nearly $600 from 2017 to 2023 ($5,253 to $4,685), before increasing by about $700 from 2023 to 2026 ($4,685 to $5,421).

In 2026, the Average Enrollment-Weighted Out-of-Pocket Limit for Medicare Advantage Enrollees Is Lower for HMOs Than PPOs

The average out-of-pocket limit faced by Medicare Advantage enrollees in 2026 is $5,421 for in-network services and $9,825 for in-network and out-of-network services combined (Figure 1). These averages are lower than the maximum allowable out-of-pocket limits ($9,250 and $13,900, respectively).

Differences in out-of-pocket limits may reflect how Medicare Advantage plans choose to allocate rebate dollars, which are extra payments they receive from the federal government beyond the cost of providing Part A and Part B services. Plans may use rebates to reduce beneficiary cost sharing, including lowering out-of-pocket limits, but they can also use these funds for other purposes, such as offering supplemental benefits not covered by traditional Medicare, offering a rebate against the Part B premium, or lowering Part D premiums.

In 2026, the Average Out-Of-Pocket Limits for Medicare Advantage Enrollees Are ,421 for In-Network Services and ,825 for In-Network and Out-Of-Network Services Combined (Bar Chart)

Out-of-pocket limits for in-network services vary by plan type. HMOs, which have 12.8 million Medicare Advantage enrollees in 2026, generally offer no coverage of services from out-of-network providers, but offer a lower out-of-pocket limit for in-network services than PPOs. PPOs, which have 8.6 million enrollees in 2026, cover services delivered by in-network and out-of-network providers, but require higher cost sharing for out-of-network providers. While PPO enrollees have broader access to out-of-network providers than HMO enrollees, they also face a higher out-of-pocket limit, even for in-network services. Specifically, the average enrollment-weighted out-of-pocket limit for in-network services is $6,592 for PPOs and $4,636 for HMOs.

The distribution of enrollment between HMOs and PPOs, as well as the average out-of-pocket caps for in-network services by type of plan, vary across states (Appendix Table 1). Due in part to PPOs (which have higher average in-network out-of-pocket limits than HMOs) comprising a larger share of enrollment in rural areas, the average out-of-pocket cap is about $800 higher for Medicare Advantage enrollees in rural areas than in urban areas ($6,078 vs $5,291).

In 2026, Roughly One in Ten Medicare Advantage Enrollees Are in Plans With Limits of $3,000 or Less for In-Network Services and About One in Five Are in Plans With Limits Above $7,000

Among all Medicare Advantage enrollees in individual plans, just over one in ten (13%, 2.8 million) are in plans with out-of-pocket limits of $3,000 or less for in-network services (Figure 2). Nearly all of these enrollees (99%) are in an HMO. More than two-thirds (68%, 14.4 million) of Medicare Advantage enrollees are in plans with out-of-pocket limits above $3,000 and up to $7,000. About one in five (19%, 4.1 million) are in plans with limits above $7,000, including 1.8 million enrollees who are in a plan with the maximum in-network out-of-pocket limit of $9,250. PPOs enrollees account for the majority of these enrollees at the maximum cap (66%).

Among the 8.6 million Medicare Advantage enrollees in PPOs, about one in ten (9%) have a combined limit for in-network and out-of-network services at or below $6,000. More than two-thirds (66%; 5.7 million) of enrollees are in plans with a combined limit for in-network and out-of-network services between $6,000 and $12,000. One quarter (25%; 2.1 million) are in plans with an out-of-pocket limit for in-and out-of-network services combined above $12,000, including 1.8 million enrollees in plans with the maximum out-of-pocket limit for in-and out-of-network services combined ($13,900) (Figure 2).

Roughly One in Ten Medicare Advantage Enrollees Are in Plans With Out-Of-Pocket Limits of ,000 or Less for In-Network Services and About One in Five Are in Plans With Limits Above ,000 (Column Chart)

Average Out-of-Pocket Limits for In-Network Services Generally Declined Between 2017 and 2023 but Have Increased Since Then

The average limit for in-network services decreased by nearly $600 from 2017 ($5,253) to 2023 ($4,685), before increasing by about $700 from 2023 to 2026 ($5,421) (Figure 3, Appendix Table 2). The average limit for in-network and out-of-network services combined has fluctuated over time but increased overall by about $750 between 2017 ($9,073) and 2026 ($9,825).

The maximum allowable out-of-pocket cap has generally increased over time, consistent with projected beneficiary out-of-pocket spending in traditional Medicare, which CMS uses to calculate maximum out-of-pocket limits in Medicare Advantage. However, the maximum cap decreased by $100 between 2025 and 2026. The average out-of-pocket limit faced by enrollees each year has always been lower than the maximum allowable limit. This gap has generally widened over time, but shrank somewhat between 2025 and 2026.

Average Out-Of-Pocket Limits in Medicare Advantage Declined Between 2017 and 2023 But Have Increased Since Then (Line chart)

Methods

This analysis uses data from the Centers for Medicare & Medicaid Services (CMS) Medicare Advantage Enrollment, Benefit and Landscape files for 2017-2026. The analysis excludes Special Needs Plans (SNPs), employer- and union-sponsored plans, PACE plans, and cost plans. These plans serve distinct populations and some may have different enrollment requirements than Medicare Advantage plans (e.g., may be available to beneficiaries with only Part B coverage) and in some cases, may be paid differently than Medicare Advantage plans, limiting comparability with individual Medicare Advantage plans for general enrollment. These exclusions are reflected in both current data as well as data displayed trending back to 2017.

The total number of enrollees in individual Medicare Advantage plans in this brief (21.3 million) may be slightly different than the number reported in other KFF briefs because this analysis further excludes a small number of plans without an in-network out-of-pocket amount specified in the plan benefits files.

The average for PPOs in this analysis includes two types of plans: local PPOs, which cover individual or multiple counties, and regional PPOs, which cover an entire state or multiple states. The average for HMOs includes two types of plans: HMOs that primarily cover services provided by in-network providers only and therefore do not have a limit for out-of-network services, and HMOs that are Point-of-Service plans (HMO-POS), which allow out-of-network care for certain services but typically charge higher cost sharing than for in-network services.

In previous years, KFF’s analysis of average out-of-pocket limits in Medicare Advantage excluded HMO-POS because they represented a relatively small share of HMO enrollment at the time (e.g., 10% in 2017). However, HMO-POS enrollment has grown substantially and now accounts for nearly half (46%) of HMO enrollment in Medicare Advantage. As a result, these plans are included in the current analysis to better reflect the experience of a substantial share of Medicare Advantage enrollees in HMOs.

This analysis determines urban and rural analysis based on the 2024 Urban Influence Codes (UIC) published by the U.S. Department of Agriculture (USDA) Economic Research Service. See Methods of KFF, “Key Facts About Medicare Beneficiaries in Rural Areas” (June 2025) for more details. Connecticut is excluded from the analysis by rurality because of differences in FIPS codes in the CMS Medicare Advantage data and the USDA 2024 UIC.

Appendix Tables

Average Out-of-Pocket Limits in Medicare Advantage by State, 2026 (Table)
Average Out-of-Pocket Limits and Maximum Out-of-Pocket  Limits, 2017-2026 (Table)

VOLUME 47

Hantavirus Outbreak Revives COVID-Era False Health Claims


Highlights

A hantavirus outbreak linked to a Dutch cruise ship in early May was followed by false health claims that mirror patterns documented in previous outbreaks, including unsupported claims that ivermectin is an effective treatment, that the outbreak was planned in advance, and that it was caused by COVID-19 vaccines.

The Monitor also examines a new analysis of Americans’ relationship with health and wellness influencers, finding that most who get health information and advice from them express skepticism about what they hear.


What We’re Watching

As Hantavirus Cases Emerged, So Did Familiar False Claims About Causes and Cures

False health claims tend to follow recognizable patterns across outbreaks, including distrust of official sources, promotion of unproven treatments, and accusations of hidden profit motives. The hantavirus outbreak linked to the Dutch cruise ship MV Hondius was no exception, with several familiar false narratives spreading alongside the official response from the World Health Organization (WHO) and other agencies:

  • Unproven Treatments: Within hours of the first headlines, a Texas otolaryngologist who became a prominent promoter of ivermectin during COVID-19 posted without evidence on May 6 that ivermectin “should work” as a hantavirus treatment because it “is a RNA virus,” claiming that ivermectin “blocks RNA viruses” from replicating in the cell nucleus. The claim overstates available evidence from some laboratory and animal studies about ivermectin’s effect on virus replication. There is no evidence that ivermectin would be effective against hantavirus, which replicates outside of the nucleus, and there is no approved vaccine or antiviral treatment for hantavirus. Former U.S. Representative Marjorie Taylor Greene shared the post, recommending ivermectin, vitamin D, and zinc to her followers as potential hantavirus treatments. The following day, the same physician offered that she would sell ivermectin without a prescription to her followers in Texas.
  • False Claims that the Outbreak Was Caused by COVID-19 Vaccines: A Pfizer document listing adverse events that had been monitored during COVID-19 vaccine trials was also misrepresented as evidence that the vaccines caused hantavirus, a claim that was also made about COVID-19 itself. The document listed conditions that researchers designated in advance as worth monitoring closely during trials, not events that were observed or confirmed to have occurred. Hantavirus pulmonary infection appeared on that list, but its inclusion reflects standard safety surveillance, not causation.
  • The “Plandemic” Narrative: While less widespread than other false health claims about the outbreak, some social media accounts framed the outbreak as a “plandemic” and evidence of a depopulation campaign, reviving narratives that circulated during COVID-19. Their posts misleadingly presented early-stage research into a potential hantavirus vaccine, announced in 2024, as proof that the outbreak was planned in advance and referred to potential vaccines as dangerous or as primarily vehicles for pharmaceutical companies to profit. In reality, research into hantavirus vaccines has been ongoing for decades because it is a known pathogen with no available vaccines.

Why This Matters: The narratives that accompanied the hantavirus outbreak are not new. Researchers and fact-checkers have documented nearly identical claims in response to COVID-19, mpox, and avian flu, often with the same accounts recycling framing across new outbreaks. Each cycle may make it harder for accurate health information to reach audiences before these false narratives spread.

Most Americans Who Follow Health Influencers Are Skeptical of What They Hear

A new Pew Research Center analysis offers a detailed look at who is producing and consuming health and wellness content on social media. Four in ten U.S. adults, and half of those under 50, say they ever get health and wellness information from social media influencers or podcasts. Yet among those audiences, trust is limited. Just one in ten say they trust all or most of what they hear from these sources, while nearly a quarter (24%) say they trust not too much or none of it. The majority, about two-thirds, say they trust some. While most (54%) say the information has helped them better understand how to be healthy, about one in eight (12%) say it has left them more confused.

Of the nearly 7,000 health and wellness influencers Pew identified on YouTube, TikTok, and Instagram, about 41% describe themselves as some kind of health care professional, a category that includes not only physicians and nurses but also chiropractors, naturopaths, and functional medicine practitioners. The remaining health and wellness influencers describe themselves as coaches, entrepreneurs, or offer little biographical information at all. Most people who get content from influencers say they come across this content passively rather than seeking it out. Certain groups, including Black, Hispanic, and Asian Americans, and those without health insurance, are more likely to turn to health influencers for information, a finding that may point to gaps in the formal health care system as a driver of influencer engagement.

The findings add context to KFF polling, which found that 55% of the public use social media to find health information or advice at least occasionally, and 14% report getting health advice regularly from social media influencers. But trust in influencers was limited in the KFF survey as well: about four in ten (39%) of those who regularly got health information or advice from influencers said those influencers were primarily motivated by serving the public interest, compared to six in ten (61%) who said they were primarily motivated by their own financial interests. As KFF President and CEO Drew Altman wrote in a “Beyond the Data” column last August, the relatively small share of people who say they regularly get health information from influencers suggests that health communicators should keep the role of influencers in perspective, at least for now.

A Closer Look at the State Level: Nearly Half of California Residents Distrust the Health Care System, But Most Trust Providers

As the 2026 midterms approach, health information and trust dynamics vary across states, shaped by local politics, demographics, and access. The Monitor will periodically examine state-specific data and trends as part of our broader tracking of the health information environment.

A survey of California residents conducted by NORC at the University of Chicago for the California Health Care Foundation (CHCF) found that 46% say they have “not much” trust in the health care system or “none at all.” But, trust varies sharply depending on who within the system is being evaluated. Nine in ten Californians say they trust nurses and more than eight in ten say they trust their personal doctor, while fewer than half (49%) trust hospital administrators and roughly a third trust health insurance companies (33%) or pharmaceutical companies (30%). The survey also found that Californians who had skipped care due to cost were significantly less likely to trust the system overall, with 35% of that group expressing at least a fair amount of trust, compared to 54% of Californians overall.

These findings are in line with past KFF polling showing that doctors and health care providers are consistently the public’s most trusted source of health information. More recently, KFF’s latest April Health Tracking Poll finds that most of the public (70%) say they trust doctors and health care providers at least “a fair amount” to act in the public’s best interest, a sentiment that is shared across partisanship.


Pennsylvania Lawsuit Challenges AI Chatbots Presenting as Licensed Medical Professionals

The state of Pennsylvania has filed a lawsuit against Character.AI, alleging that its platform enabled chatbots to present themselves as licensed medical professionals and provide medical advice without proper credentials. According to the complaint, the chatbot claimed to be a psychiatrist licensed in Pennsylvania and offered mental health guidance, including discussion of diagnosis and treatment options, while using a fabricated license number. State officials argue this constitutes the unlawful practice of medicine. The company has said that its characters are fictional and accompanied by disclaimers indicating they are not real professionals, but the case raises questions about the effectiveness of such safeguards when users engage with highly personalized AI systems in vulnerable moments. The lawsuit arrives as the safety and accuracy of AI chatbots in the context of mental health is drawing increased scrutiny. KFF’s March 2026 Tracking Poll on Health Information and Trust found that about one in six adults had used AI chatbots in the past year for mental health information and advice, and a majority (58%) of those who did said they did not follow up with a mental health professional.

The American Medical Association (AMA) released a new policy framework calling for stronger legal protections against AI-generated “deepfakes” that impersonate physicians through fake videos, audio, or images. The group warned that manipulated content falsely showing doctors endorsing treatments or giving medical advice could mislead patients, damage trust in physicians, and spread unproven or harmful health information, particularly as AI-generated misinformation becomes more realistic and harder to detect, even by trained medical professionals. 

The AMA’s proposal calls for explicit opt-in consent before a physician’s likeness, voice, or identity can be used in AI-generated content, mandatory labeling and digital watermarks for synthetic media, and faster takedown and enforcement mechanisms. It also calls for shared responsibility among hospitals, platforms, and AI companies for preventing impersonation. The policy reflects growing concern within medicine about how generative AI tools could be used to exploit the credibility of health professionals online.

About The Health Information and Trust Initiative: the Health Information and Trust Initiative is a KFF program aimed at tracking health misinformation in the U.S., analyzing its impact on the American people, and mobilizing media to address the problem. Our goal is to be of service to everyone working on health misinformation, strengthen efforts to counter misinformation, and build trust. 


View all KFF Monitors

The Monitor is a report from KFF’s Health Information and Trust initiative that focuses on recent developments in health information. It’s free and published twice a month.

Sign up to receive KFF Monitor
email updates


Support for the Health Information and Trust initiative is provided by the Robert Wood Johnson Foundation (RWJF). The views expressed do not necessarily reflect the views of RWJF and KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities. The data shared in the Monitor is sourced through media monitoring research conducted by KFF.

News Release

Drew Altman, Founding President and CEO of KFF, Announces Retirement Plans; Board Appoints Larry Levitt and Mollyann Brodie as Next Leadership Team

Dr. Altman has led the organization for nearly 40 years; Levitt and Dr. Brodie to assume leadership roles next year, after a combined six decades at KFF in senior positions guiding policy research and polling

Published: May 27, 2026

After nearly 40 years shaping the national health policy landscape and leading it through pivotal debates, KFF announced today that Dr. Drew Altman will retire from his role as Founding President and Chief Executive Officer on December 31. KFF’s Board of Trustees has appointed Larry Levitt and Dr. Mollyann Brodie as the new leadership team. Beginning in 2027, Levitt and Dr. Brodie will assume the leadership positions of CEO and President, respectively.

Since Dr. Altman founded the modern-day KFF, coming to California in 1990 to establish it from what once was the Henry J. Kaiser Family Foundation, the organization has become the nation’s leading source of health policy analysis, polling, and news. Under his leadership, KFF has evolved into a one-of-a-kind information organization, bringing together policy research, polling and survey research, and journalism, most recently through the creation of KFF Health News, the nation’s largest health policy newsroom. There is no organization in the country that has played a more pivotal role in informing policymakers, the media, and the public with data-centered analysis about U.S. health policy.

“Building KFF over the last three plus decades has been a mission for me,” said Dr. Drew Altman, Founding President and Chief Executive Officer of KFF. “My whole purpose has been to build an institution that could be a force for people and for truth in health care, and we’ve achieved that and more. Together, we have built an organization that combines policy research, polling, and news all in one, a new kind of information organization. I’m immensely proud of that legacy and KFF’s role at the highest levels of health policy. Larry and Molly each play a central role as KFF’s executive team now and have for years, and I have complete confidence in their leadership, in KFF’s remarkable staff who do our work, in our Board, and in KFF’s future.”

“With two small grandkids in Sacramento and Atlanta and another on the way, after what will be almost 37 years of very hands-on leadership since I founded KFF, and with KFF at the apex of its effectiveness, and the opportunity for a perfect transition, the clock in my head is telling me it’s time,” Dr. Altman added.

“KFF is the most trusted and respected voice in health policy, in large part because of Drew Altman and his vision and leadership. During my time in the U.S. Senate, the organization’s data and research were invaluable in shaping key health care decisions, underscoring the impact of KFF’s work, and the organization continues to play a unique and monumental role today,” said former U.S. Senator Olympia Snowe, Chair of KFF’s Board of Trustees. “Recognizing this is a pivotal moment for KFF, the Board engaged in a lengthy succession planning process, which was deliberative and thoughtful. Based on our governance considerations, the Board identified two exceptional leaders, Dr. Mollyann Brodie and Larry Levitt, who not only know this organization, but who have helped it grow and evolve into what it is today. We therefore selected Larry and Molly to serve as CEO and President, respectively. As we look to the future of KFF, Molly and Larry’s deep experience, understanding of KFF, and their unwavering commitment to its mission make them the best team to guide us into an exciting next chapter.”

Under Dr. Altman’s leadership, KFF has been a cornerstone of the nation’s health policy and health journalism landscapes—anchoring pivotal debates with rigorous, nonpartisan data analysis and reporting. Its work has informed understanding of landmark policies, including key provisions of the Affordable Care Act, Medicaid, and Medicare, and provided essential context during moments of crisis, such as the COVID-19 pandemic, when its COVID Vaccine Monitor and reporting became vital resources used around the country. Since the 1990s, KFF’s data and analyses have helped illuminate the real-world implications for people of proposals like Medicaid block grants, ensuring that policymakers and the public alike are equipped with credible, evidence-based insights.

Following the recommendation of a search committee led by Board Vice-Chair Jim Canales, KFF’s Board unanimously appointed Levitt and Dr. Brodie as incoming CEO and President, respectively. Both have served as Dr. Altman’s executive team for over a decade. Levitt, who will take over as CEO, currently serves as Executive Vice President for Health Policy, overseeing KFF’s policy analysis of programs including Medicare, Medicaid, the Affordable Care Act, women’s health, racial equity, global health, and more. Dr. Brodie currently serves as Executive Vice President and Chief Operating Officer, overseeing KFF’s operations and leading its nationally recognized Public Opinion and Survey Research Program, and recently received the American Association of Public Opinion Research’s Award for Exceptionally Distinguished Achievement for her professional accomplishments in the field. She will assume the role of President. Levitt and Dr. Brodie will both serve on the Board.

“We are grateful for Drew’s vision in establishing KFF as a leading source for independent and nonpartisan health policy information and look forward to continuing that mission,” said Dr. Molly Brodie, incoming President of KFF, and Larry Levitt, incoming Chief Executive Officer of KFF, in a joint statement. “We appreciate the vote of confidence in us by KFF’s Trustees and are excited to work together to lead an organization of immensely talented and professional staff.”

“With ongoing debates over affordability and other important health policy issues, KFF will continue to bring to the table timely and credible facts through our trusted research and journalism,” said Levitt. “We will build on the credibility KFF has established as an independent and nonpartisan source of health policy information in an increasingly polarized environment.”

“KFF will continue our laser focus on how health policies and the health care system affect real people,” said Dr. Brodie. “We are committed to leading KFF as a trusted source of information in an era of declining trust in public and private health care institutions.”

Dr. Altman will continue to work closely with Dr. Brodie and Levitt to ensure a smooth transition. He will continue in his role as President and CEO through the end of 2026, with Levitt and Dr. Brodie assuming their new leadership roles in January 2027.

Key Facts About Health Care Affordability for People With Medicare

Published: May 27, 2026

Health care costs and affordability recently topped the public’s list of economic anxieties in the U.S., according to KFF polling. Even people with insurance say they struggle to afford health care costs, including people with Medicare. While Medicare provides health insurance coverage to 70 million people age 65 or older and younger adults with long-term disabilities, having Medicare coverage does not insulate beneficiaries from health-related affordability challenges, such as not getting needed medical care due to costs or incurring medical debt. In a 2026 KFF Health Tracking Poll, half (49%) of all Medicare beneficiaries ages 65 and older say they expect their health care costs to become less affordable in the next year.

This brief presents key facts and analysis about affordability of health care costs among people with Medicare, including younger adults with long-term disabilities, drawing on data from various sources (see methods for additional information).

Many Medicare Beneficiaries Have Low Incomes and Modest Savings, Which Can Make It Hard To Afford Medical and Long-Term Care Services

  • One in four Medicare beneficiaries (16.5 million people) had income below $24,600 per person in 2024, or about 160% of the federal poverty level that year (Figure 1). These estimates take into account income from Social Security, pensions, retirement account (IRA) withdrawals, and other sources. At the upper end of the income spectrum, the top 5% of Medicare beneficiaries (3.3 million people) had incomes above $169,700 per person. Many beneficiaries also have relatively low levels of savings, with one in four Medicare beneficiaries having savings below $18,950 per person in 2024. Financial resources are even lower among some subgroups of beneficiaries, including Black and Hispanic beneficiaries. For example, one in four Black beneficiaries had income below $20,150 per person in 2024, while one in four Hispanic beneficiaries had income below $14,150 per person.
One in Four Medicare Beneficiaries Lived on Incomes Below ,600 Per Person and Half Lived on Incomes Below ,200 Per Person in 2024 (Line chart)
  • About 6 million people ages 65 and older (10%) were living in poverty in 2024 under the official poverty measure, meaning they had income of $15,050 or less that year (if single), while 17.3 million (28%) had incomes below 200% of poverty. Poverty rates among older adults are higher under an alternative measure (the supplemental poverty measure, or SPM) that accounts for certain expenses that are higher among older people, including out-of-pocket medical expenses, with 15% of older adults living in poverty in 2024 under the SPM.
  • In 2025, nearly a quarter (23%) of all Medicare beneficiaries who received Social Security benefits relied on Social Security income for 90% or more of their total per capita income, while about one-third (32%) relied on Social Security for at least 75% of their income (Figure 2). In 2025, the average per capita Social Security income was $20,168 among those who depended on Social Security for at least 90% of their income and $20,670 among those who depended on Social Security for at least 75% of their income.
Figure 2

Medicare Premiums and Other Health Expenses Consume a Sizeable Portion of Income and Household Budgets for People With Medicare

  • Out-of-pocket health care spending for Medicare premiums and out-of-pocket costs for health care services accounted for 36% of Medicare beneficiaries’ average Social Security income per person in 2023 (Figure 3). In 2023, Medicare beneficiaries spent an average of $6,459 out of pocket on health care costs and had average Social Security income of $17,718 (though most older adults have other sources of income beyond Social Security that can be used to pay their out-of-pocket health care costs). Out-of-pocket spending includes premiums for Medicare supplemental coverage (Medigap) for those who enroll in traditional Medicare and buy private supplemental insurance.
Figure 3
  • Health care spending accounted for 14% of Medicare beneficiaries’ total household spending in 2024. Medicare households spent a larger share of their total household spending on health care than non-Medicare households in 2024 (6%) (Figure 4).
Health Care Accounted for a Larger Share of Total Household Spending for Medicare Households Than for Non-Medicare Households in 2024 (Stacked Bars)
  • More than 7 million Medicare beneficiaries enrolled in Medicare Part B in 2024 spent more than 10% of their annual per capita income on Part B premiums alone. The standard Part B premium is paid by beneficiaries in both traditional Medicare and Medicare Advantage and has roughly doubled in the last decade, from an annual amount of $1,259 in 2015 to $2,435 in 2026.

The Choice Between Traditional Medicare and Medicare Advantage Has Cost Implications for Beneficiaries

  • Out-of-pocket spending for Medicare-covered hospital and physician services is not capped in traditional Medicare, while Medicare Advantage plans are required by law to provide an out-of-pocket limit for these services. In 2025, the average out-of-pocket limit for Medicare Advantage enrollees was $5,320 for in-network services and $9,547 for in-network and out-of-network services combined. The maximum allowed limits were $9,350 for in-network services and $14,000 for in-network and out-of-network services combined in 2025, and increased to $9,250 and $13,900, respectively, in 2026. (Figure 5). This cap protects Medicare Advantage enrollees from unlimited health care costs for Medicare-covered services, but cost-sharing requirements can lead to high out-of-pocket expenses before reaching a plan’s annual limit. People enrolled in Medicare Advantage plans typically pay no additional premium.
In 2025, the Average Out-Of-Pocket Limits for Medicare Advantage Enrollees Were ,320 for In-Network Services and ,547 for In-Network and Out-Of-Network Services Combined (Bar Chart)
  • Medicare Advantage plans can reduce cost sharing, offer benefits not covered under traditional Medicare (such as dental and vision services), and lower Part B and Part D premiums, using extra payments they receive from the federal government beyond the cost of providing Part A and Part B services. In 2026, these extra payments (known as rebates) amounted to about $2,660 per person on average in 2026. For Medicare-covered services under Part A and Part B, Medicare Advantage plans can charge different amounts than what someone in traditional Medicare would pay, though they often reduce cost sharing for Medicare-covered benefits, and they are prohibited from charging more for certain services, such as Skilled Nursing Facility (SNF) stays. Plans are required to provide coverage that is at least as generous overall as traditional Medicare, even though what enrollees pay out of pocket can vary depending on the type of plan, the type and quantity of services they use, and whether they see a provider that participates in the plan’s network.
The Average Monthly Medigap Premium Across All Current Medigap Policyholders Was 7 and Varied Across States, Ranging From 1 in Alaska to 7 in New York (Choropleth map)
  • More than 3 million Medicare beneficiaries in traditional Medicare have no additional coverage that helps with Medicare cost-sharing requirements, such as Medigap, employer coverage, or Medicaid. This leaves them at risk of facing high out-of-pocket costs if they need a lot of medical services, or high-cost services, because there is no limit on out-of-pocket spending for Parts A and B in traditional Medicare.

Paying for Health Care, Including for Services Not Covered by Medicare, Can Be a Financial Burden

  • Medicare beneficiaries can face high out-of-pocket costs for dental, hearing, and vision care services, which are not covered under traditional Medicare (Figure 7). In 2023, traditional Medicare beneficiaries spent $1,107 on dental services and $564 on hearing services, on average (Figure 7). While most Medicare Advantage plans cover dental, hearing, and vision benefits, Medicare Advantage enrollees also face out-of-pocket costs for these services, spending an average of $571 on dental services and $212 on hearing services.
Traditional Medicare Beneficiaries Can Face High Out-Of-Pocket Costs for Services Not Covered by Medicare (Bar Chart)
  • About one in five (22%) Medicare-age adults reported having some type of debt as a result of medical or dental bills in 2022 (Figure 8). Among older adults with medical debt, about 4 in 10 say they cut back on other household spending and used up or all or most of their savings as a result of their health care debt.
One in Five Adults Age 65 and Older Report Experiencing Debt Due to Medical or Dental Bills (Bar Chart)
  • Long-term services and supports, which are not covered by Medicare, are unaffordable for all but the highest-income Medicare beneficiaries. In 2025, the median annual costs of common long-term services and supports in the U.S were $80,080 for full-time non-medical caregiver services (including home health aide and homemaker services for people who need help with instrumental activities of daily living such as preparing meals and doing laundry), $129,575 for a private room in a nursing home, and $305,760 for round-the-clock home health aide services (Figure 9). These costs greatly surpass median income ($43,200) and savings ($110,100) among people with Medicare. Long-term care services are generally not covered by Medicare, regardless of whether a beneficiary is enrolled in traditional Medicare or Medicare Advantage.
Median Annual Costs of Common Long-Term Services and Supports, Generally Not Covered by Medicare, Exceed the Median Income of Medicare Beneficiaries (Column Chart)

Medicaid Helps Make Medicare Affordable for About 12 Million Low-Income Medicare Beneficiaries

  • In 2025, about 12 million people with Medicare also had Medicaid coverage (“dual-eligible individuals”).
    • More than seven in ten (72%) dual-eligible individuals, or 8.5 million people, are eligible for the full range of Medicaid benefits not otherwise covered by Medicare, including long-term services and supports, vision and dental services, and non-emergency medical transportation (also known as wraparound services) (Figure 10).These “full-benefit” dual-eligible individuals also usually receive additional help through the Medicare Savings Programs (MSPs), which cover Medicare premiums, and in most cases, cost sharing for people with limited income and assets.
    • The remaining 3.4 million dual-eligible individuals (“partial-benefit” individuals) do not receive coverage of the full range of Medicaid benefits, but do receive payments to cover Medicare premiums, and, in most cases, cost sharing through the Medicare Savings Programs. Under federal guidelines, Medicare beneficiaries with income up to 135% of the federal poverty line and assets below specified levels ($9,950 for an individual and $14,910 for a couple in 2026) qualify for financial assistance from their state Medicaid program through a Medicare Savings Program. States can choose to cover Medicare beneficiaries with income or assets above the federal limits, and in 2026, 18 states do so. Without financial support from Medicaid, the Part B premium alone would consume 15% of income for a dual-eligible individual with monthly income of $1,350, not including other out-of-pocket costs.
Medicaid Helps Make Medicare Affordable for About 12 Million Medicare Beneficiaries, Most of Whom Are Eligible for Wraparound Services Not Covered by Medicare (Donut Chart)

Medicare Part D Offers Protection Against High Out-of-Pocket Prescription Drug Costs, but Prescription Drug Costs Remain a Concern for Older Adults

  • Virtually all Medicare beneficiaries (96%) use prescription drugs and most are enrolled in Medicare Part D drug plans for prescription drug coverage. On average, Medicare Part D enrollees who did not receive low-income subsidies spent an average of $872 on prescription drugs in 2023, and people in fair or poor health spent roughly twice as much, on average ($1,671) (Figure 11). The Part D low-income subsidy (LIS) provides substantial financial support to income below 150% of poverty (under $23,940 for an individual in 2026) and limited assets (under $18,090 for an individual). Part D enrollees with LIS had average out of pocket drug costs of $156 in 2023, roughly one fifth the amount paid by those without these low-income subsidies.
Medicare Part D Enrollees Who Did Not Receive Low-Income Subsidies Spent an Average of 2 on Prescription Drugs in 2023, and Those in Fair or Poor Health Spent Roughly Twice as Much (Split Bars)
  • Under changes made by the Inflation Reduction Act, Part D enrollees have a cap on out-of-pocket drug spending equal to $2,100 in 2026. Prior to this change, enrollees could have faced several thousand dollars in out-of-pocket costs for expensive medications each year. The Inflation Reduction Act also includes other changes that make prescription drugs more affordable for people with Medicare, including a $35 monthly cap on insulin, expanded eligibility for full benefits under the Part D Low-Income Subsidy, and $0 cost sharing for adult vaccines under Medicare Part D. Additionally, the law requires the federal government to negotiate lower drug prices for some high-cost drugs covered under Medicare through the Medicare Drug Price Negotiation Program.
  • Even with a cap on overall out-of-pocket costs, prescription drug costs are a concern for Medicare beneficiaries, with half (50%) of Medicare beneficiaries age 65 and older worried about being able to afford prescription drugs for themselves or their family in 2026, according to a March 2026 KFF health tracking poll.

The Growth in Medicare Spending Will Lead to Higher Medicare Premiums, Deductibles, and Copayments Over Time

  • People with Medicare will face higher premiums and other out-of-pocket costs for Medicare benefits over time since Medicare premiums and deductibles are directly tied to increases in spending on Medicare-covered services. Higher Medicare spending is driven in part by rising prices, higher utilization, and growth in spending on Medicare Advantage. Between 2026 and 2034, the Medicare Part B premium and deductible are projected to increase by roughly 70%—from $2,435 to $4,170 for the Part B premium (annualized) and from $283 to $486 for the Part B deductible, while the Part A deductible is projected to grow by about 30% (from $1,736 to $2,212) (Figure 12).
People With Medicare Are Projected to Face Rising Cost Sharing, With the Part B Premium and Deductible Projected to Increase by About 70% From 2026 to 2034 (Line chart)
  • Rising Medicare premiums and cost sharing will consume a growing portion of Medicare beneficiaries’ financial resources. On average, premiums and cost sharing for Medicare Part B and Part D accounted for 25% of the average Social Security benefit in 2025, and this share is projected to increase to 33% in 2040. Including other premium and cost-sharing amounts would increase these shares even further, though as noted earlier most older adults can tap other sources of income beyond Social Security to pay for health care expenses.

Methods

This brief draws on data from various sources. Data on income and savings of Medicare beneficiaries, including the share of beneficiaries who relied on Social Security for at 75% or 90% or more of their total per capita income and the number of Medicare beneficiaries who spent more than 10% of their annual per capita income on Part B premiums, are drawn from the Urban Institute’s Dynamic Simulation of Income Model (DYNASIM4). See Methods of KFF, “Income and Assets of Medicare Beneficiaries in 2024” (August 2025) for more details.

Data on out-of-pocket health care spending are from the Centers for Medicare & Medicaid Services (CMS) Medicare Current Beneficiary Survey, 2023 Cost Supplement File (the most recent year of data available). For the analysis on average out-of-pocket spending as a share of average per capita Social Security income, see the methods of KFF, “Health Costs Consume a Large Portion of Income for Millions of People with Medicare” (August 2025) for more details.

The 2024 Consumer Expenditure Survey (CE) by the Bureau of Labor Statistics is used to assess the financial burden of health care spending among households where all members are covered by Medicare (referred to as Medicare households) compared to households where no members are covered by Medicare (referred to as non-Medicare households). The CE is a survey of households (“consumer units”), excluding people residing in institutions such as long-term care facilities. The estimates presented in this analysis are averages for demographic groups of consumer units, not per capita estimates, and thus are not comparable to estimates based on other surveys that report per capita estimates, such as out-of-pocket health care spending reported in the Medicare Current Beneficiary Survey. 

Estimates of Medigap premiums are based on KFF analysis of Medicare Supplement Market Data from Mark Farrah Associates Health Coverage Portal TM, 2023. See methods of KFF, “Key Facts About Medigap Enrollment and Premiums for Medicare Beneficiaries” (October 2024) for more details.

Data on annual Medicare premiums, deductibles, and other cost sharing over time are based on KFF analysis of the 2025 Annual Report of the Boards of Trustees of the Federal Hospital Insurance and Federal Supplementary Medical Insurance Trust Funds.

This work was supported in part by The John A. Hartford Foundation. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

The Medical Frailty Exemption from Medicaid Work Requirements: Key Issues to Watch for in Upcoming CMS Guidance

Published: May 27, 2026

For the latest analysis on the medical frailty exemption and key takeaways from the published interim rule, see our updated brief.

The 2025 reconciliation law requires states to condition Medicaid eligibility for adults in the Affordable Care Act (ACA) Medicaid expansion group and enrollees in partial expansion waiver programs (Georgia and Wisconsin) on meeting work requirements starting January 1, 2027 or sooner at state option. The law specifies mandatory exemptions, including individuals who are “medically frail.” To ease the burden on individuals, the law directs states to use available information “where possible” to verify compliance with Medicaid work activities or exemption status, without requiring additional documentation from individuals. Given the abbreviated implementation timeline, states are moving forward with key decisions over how to implement the medical frailty exemption even as they wait for formal guidance from the Centers for Medicaid and Medicare Services (CMS), which is required to issue an interim final rule by June 1, 2026. This brief describes early state plans to operationalize the medical frailty exemption and identifies key issues that they are facing and may be answered in the forthcoming guidance.

What is the Medical Frailty Exemption?

The reconciliation law requires states to exempt from work requirements an individual who is “medically frail or otherwise has special medical needs.” The law specifies this includes individuals who are blind or disabled; have a physical, intellectual, or developmental disability that limits their ability to perform one or more activities of daily living (ADL); have a substance use disorder or a “disabling” mental disorder; and those with “serious or complex” medical conditions. This definition closely aligns with an existing federal medical frailty definition that CMS uses for states choosing to set “alternative benefit plans” that differ from the traditional Medicaid benefit package. In that context, CMS used the definition as a minimum standard for medical frailty but allows states flexibility to define medical frailty beyond the statutory and regulatory definitions. To identify individuals who are medically frail, CMS noted in the 2013 final rule that it expected states to use Medicaid claims data and encouraged them to use self-attestation and health screeners for applicants and new enrollees where the state does not have information on their current health status or historic encounter data.

How do States Plan to Operationalize the Medical Frailty Exemption?

Most states have not yet finalized a medical frailty definition, likely reflecting ongoing uncertainty over how much flexibility states will have as they await June CMS guidance. In a recent KFF survey (fielded January-March 2026), about half of states (22) subject to work requirements report having a current state medical frailty definition, though it is unclear whether these definitions align with the medical frailty provisions in the reconciliation law (Figure 1). Most of these definitions were not developed with work requirements in mind and may need to be updated to reflect the new federal requirements. Thirty-three states indicated they had not yet determined what definition they plan to use at the time the survey was fielded. If states are given flexibility by CMS to define who is medically frail and exempt from work requirements, six states would prefer to use a state definition (either an existing definition or a new definition,) while four states would use a federal definition.

Medically Frail Definition States Plan to Use (if CMS Allows Flexibility), March 2026 (Choropleth map)

States plan to use a variety of methods to verify medical frailty status, including using data to automate the process where possible. Most states reported plans to use Medicaid claims data (32) to verify medical frailty exemption status, while Georgia indicated it would not use claims data, and the remaining ten states had not yet made a decision at the time of the survey. New applicants and recent enrollees may not have claims data on file, requiring states to use other forms of verification.  All 32 states reporting plans to use claims data also reported plans to use other sources, such as data from other programs (e.g., enrollment in a behavioral health managed care plan or HCBS program), managed care utilization or claims data, and/or managed care case management data. Twenty-nine states said they will seek confirmation from a treating provider. Many states are developing health assessment screeners to collect information to identify medical exemptions, and 11 states said they will use the health screeners to verify medically frail status. Most states (30) also reported wanting to allow applicants and enrollees to self-attest to their medically frail status if verification data are not available and self-attestation is permitted by CMS. However, some states reported they do not plan to accept self-attestation (AR, HI, IN, MT) or have since passed legislation barring the use of self-attestation (NC and UT).

Verification Sources States Plan to Use for Medical Frailty Exemptions, March 2026 (Stacked Bars)

Nebraska, which became the first state to implement new work requirements on May 1, 2026, has released resources outlining how it will process medically frail exemptions, as well as an index of diagnosis and procedure codes. Examples of conditions covered in the thousands of codes include types of cancer, HIV, diabetes, heart disease, and certain types of mental health conditions and substance use disorders, among others. For existing enrollees, Nebraska is reviewing medical claims data prior to renewal and will auto-exempt an individual if indicated based on diagnosis/procedure codes. If Nebraska cannot determine medical frailty through claims data or other data sources, existing enrollees will need to submit a self-declaration form. Not all individuals will be able to be auto-exempted due to limitations of claims data such as:

  • A lack of data on file for new applicants and recent enrollees;
  • A lack of data on file due to providers not consistently coding or not using the codes identified by the state;
  • Selected diagnoses and procedures potentially not being comprehensive of all individuals with target conditions or not capturing functional limitations;
  • A lack of claims within the look-back period despite an individual having an exempted chronic condition or disability; and
  • Delays between clinical care and claims presenting.

The state also intends to use the self-declaration form to identify medically frail exemption status for new applicants. The self-declaration form requires individuals to provide a description of their health condition, the contact information of their treating provider, and a note if services were provided while enrolled in Medicaid. No additional documentation is required at this time (e.g., a note from a provider or other proof of a condition). Nebraska indicates that it plans to move from self-declaration to more automated verification methods consistent with federal guidance over time, and plans to continue to review and update the index of ICD-10, CPT, and HCPCS codes as federal direction is clarified.

Early insights from other states highlight the variety of ways states are planning to use multiple sources of information to identify medical frailty. For example:

  • California plans to automatically exempt individuals who are eligible for certain programs (e.g., home care—also known as home- and community-based services or HCBS) and has been exploring more timely data sources such as managed care plan care management systems in conjunction with evaluating which diagnostic codes could be used to establish medical frailty.
  • Pennsylvania has outlined a plan to first check health care claims, followed by information from electronic health records exchanged through regional health information organizations, managed care organization (MCO) health assessments and case management information, and finally information provided by the applicant. Pennsylvania explains its approach is designed with data limitations in mind, and aims to reduce paperwork burden and streamline the process for beneficiaries.
  • South Dakota has shared early plans to use clinical code lists and a medically frail health screener. Indicating lingering uncertainty on CMS’s stance regarding self-attestation, the state notes it may have to use physician attestation at renewal if screeners cannot be repeated and claims data is still not available.
  • Several states also have reported that they would be interested in adding new categories such as homelessness to the medical frailty category but understand from communications with CMS that states may not have flexibility to do so.

How Will the CMS Guidance Address Key Issues and Potential Implications?

Although states are moving forward with operationalizing the medical frailty exemption, the interim final rule that CMS is required to release by June 1, 2026, is expected to address key issues related to defining and verifying medical frailty. Because of the time required to make system changes, states have been moving forward with implementing work requirements based on informal communication and guidance CMS has shared. Any significant changes to that informal guidance could require states to change course and could have implications for states’ readiness to implement work requirements as well as the costs associated with implementation. Key issues that may be addressed in the guidance, and that states report waiting on, include:

Defining Medical Frailty

  • Defining medical frailty. CMS may provide a federal definition of medical frailty in the guidance. The law suggests the need for a Secretary-provided definition in its list of exemptions by including anyone “who is medically frail or otherwise has special medical needs (as defined by the Secretary).” It is not clear if CMS will rely on the existing definition or develop a new definition that more directly relates to work requirements. The statute includes people who are both medically frail and those with “serious or complex medical conditions,” which includes people with significant medical needs that may or may not limit their ability to engage in qualifying activities. For these individuals maintaining access to health coverage protects against serious health consequences if treatment is interrupted and may enable them to work.
  • State flexibility to define medical frailty. Whatever federal definition CMS establishes, another important consideration is whether the definition serves as a minimum standard that states can use or expand on or whether CMS will require states to use the federal definition with little or no flexibility to interpret how it will be applied. For example, CMS may specify a set of diagnoses codes for states to use in their claims data analysis, but the effect of that list will depend greatly on whether states are allowed to add additional codes to CMS’ list. This may be particularly relevant in states that use state-specific diagnosis or treatment codes in their Medicaid billing systems. 
  • Identifying people with functional limitations and mental health conditions. As noted, the law required people “with a physical, intellectual or developmental disability that significantly impairs their ability to perform 1 or more activities of daily living” be exempted. Guidance may provide additional insight into how states are expected to capture functional limitations in medical frailty definitions, as it may prove more difficult to identify these individuals using claims data. While there is a diagnostic code that could help to capture this, it is generally underutilized, with one barrier being a lack of financial incentive. More comprehensively identifying enrollees with these functional disabilities may require technical assistance for states and providers (i.e. in terms of utilizing different codes). Guidance may also provide clarity on identifying individuals with mental health conditions who may also be difficult to identify using claims data, as well as provide clarity on the exact diagnoses that would qualify.

Verifying Medical Frailty

  • Data sources for verifying medical frailty. States will likely be expected to use claims data to automate identification of medically frail individuals. The guidance may provide information on other data sources states can use or would be expected to use, such as electronic health records, MCO health assessments and case management information, and pharmacy data. States may also be required to use SNAP data and other program data, such as HCBS enrollment or enrollment in a behavioral health managed care program, to identify medically frail individuals. Accessing some of these data sources may raise privacy concerns that the guidance may or may not address.
  • Data look-back. The guidance may also specify the length of time states are permitted to look back to identify individuals with qualifying conditions when using data or verification from providers, including whether there are different look-back periods permitted at application versus renewal. The length of the look-back period will affect how many individuals are captured under the medically frail exemption (longer look-back periods are likely to pick up more people who may qualify as medically frail).
  • Exemption re-verification. The legislation does not currently clarify how frequently medical frailty exemptions may last before states are expected to re-verify individuals’ exemption status. States may need to reverify exemption status at every renewal, or states may be able to create an internal flag and/or permanently exempt some people if their health condition or disability status is unlikely to change.
  • Self-attestation. It is unclear if states will be permitted to accept self-attestation or if they will be prohibited from using it (altogether or in certain circumstances). Some state officials have noted the limitations of existing data sources, particularly claims data, for identifying new applicants who are medically frail as well as enrollees at their first renewal. Self-attestation could be subject to CMS audits, and guidance may outline under what circumstances states are expected to use self-attestation (e.g., only initial application, at renewal). If self-attestation is permitted, questions remain whether attestation alone will suffice or whether enrollees will be required to also provide supplemental information (e.g. provider sign-off, clinical or pharmacy records, etc.).
  • Health screeners. States may look to use health screeners at application and renewal, especially in the absence of self-attestation. States may have flexibility to create their own health screeners, or there may be a federal template.
  • Confirmation from providers. When using provider verification, the guidance may specify any requirements, including what information must be collected and whether providers will be required to assess whether an individual’s condition limits their ability to work. Relying on provider confirmation could increase administrative burden (on the clinical workforce, individuals, and states), particularly for providers that treat large shares of Medicaid patients, and, depending on the information requested, could raise ethical concerns among providers.
  • Exemption hierarchy. When individuals qualify under multiple exemptions or when they would qualify for a medical frailty exemption but also are engaged in qualifying work activities, states will need to develop standards for how to operationalize which status is prioritized (e.g., checking exemption status and work status in a specified order, choosing to use whichever is longer lasting), especially if certain conditions will have longer exemption periods. The guidance may establish a hierarchy for states to follow or may give states the ability to set their own hierarchies.