ACA Marketplace Enrollment is Down in 2026—But All of the Data Isn’t in Yet

Authors: Justin Lo, Jared Ortaliza, Emma Wager, Matt McGough, and Cynthia Cox
Published: Feb 5, 2026

2026 marks the first year since 2020 that enrollees in the Affordable Care Act Marketplaces do not have access to enhanced premium tax credits. The effect of the expiration on how many people will use ACA Marketplace coverage remains unclear.

New data released by CMS on plan selections show that ACA sign-ups for 2026 are down by over 1 million people compared to the same time last year, marking the first year since 2020 that sign-ups appear to have declined. A more detailed Health Insurance Exchanges Open Enrollment Report is expected in March or April that will detail demographics, income, and metal levels for people who select or are automatically renewed into a plan. Plan selection data is unable to fully capture the effects of the enhanced tax credits expiring on the number of people with coverage. As some people end up not making their premium payments, actual enrollment—known as “effectuated” enrollment—will inevitably decline. With the expiration of enhanced premium tax credits, premium payments are estimated to have increased 114%, on average, for subsidized enrollees who stay in the same plan. With such steep increases, it is not yet clear how many people who have selected a plan during Open Enrollment will make a payment. 

This brief explains the limitations of early data in understanding the impact of the expiration of enhanced premiums tax credit on ACA enrollment. It also provides a timeline of when more complete data will become available. The bottom line is that it will be quite a while before we get a complete picture of how much enrollment has dropped following expiration of the enhanced premium tax credits.

What are the limitations of plan selection data?

Plan selection (or “sign-up”) data does not accurately reflect the number of people who ultimately have ACA Marketplace coverage because it does not account for premium payments. In other words, it shows how many people have selected a plan or been automatically renewed into ACA coverage, but it does not show how many people actually gain or maintain coverage.

New enrollees are generally required to submit their first premium payment (“binder” payment) within 30 days of the coverage effective date, thus “effectuating,” or beginning, their coverage. Returning subsidized customers, however, are generally given a 3-month grace period for nonpayment of premiums. This means that these returning consumers would then have until March 31, 2026, to catch up on premium payments before their coverage is retroactively terminated. The impact of enhanced subsidies expiring will therefore not be evident (even to insurers) until all applicable grace periods have been exhausted.

For 2026, nearly 20 million of the plan selections are returning customers. Plan selection data from 2025 shows that more than four in ten people in the ACA Marketplaces were automatically renewed into their coverage that year, meaning they did not actively sign up for their plan. As consumers automatically renewed for 2026 received their first premium bills for January, some may have disenrolled or stopped making a payment. Depending on what action they take and the timing, many people could be counted in preliminary plan selection data (in the “Final Snapshot” just released and the “Open Enrollment Report” in the spring) even though they may not truly have coverage.

When will we know more about ACA enrollment?

Below is a timeline of key ACA Marketplace deadlines and data releases. The data timing listed below is based on recent years’ release dates and there could be different dates in 2026. The section following the timeline explains each of these data sources in detail.

TimingDeadline or Data Release
January 15, 2026End of Open Enrollment in most states
January 28, 2026Final Marketplace Open Enrollment Period Report: National Snapshot (plan selections) in most states; preliminary data are included for states with later open enrollment periods
January 30, 2026Last possible payment due date for January 1 enrollments in new plans
January 31, 2026End of Open Enrollment in all states
March 2, 2026Last possible payment due date for February 1 enrollments
March 31, 2026Payment grace period ends for automatic renewals processed December 15
March/April 2026*CMS Health Insurance Exchange Open Enrollment Report and Public Use Files (plan selections)
April/May 2026Public insurer first quarter earnings reports
May/June 2026Earliest 2027 insurer rate filings to state regulators become public
July 2026*Effectuated Enrollment: Early 2026 Snapshot
January 2027*Biannual National Health Interview Survey (NHIS) Early Release Data
July 2027*Effectuated Enrollment: Full Year 2026—accounts for grace period retroactive terminations
July 2027*Finalized HHS Risk Adjustment Program State-Specific Data; additional rate filings
July 2027*Issuer Level Enrollment Public Use File
2028*Enrollee-Level External Data Gathering Environment (EDGE) data

*Note: Timing is based on recent years and may change for plan year 2026.

Effectuated Enrollment

The effectuation rate is the share of people who have a plan selection during Open Enrollment who effectuate (or start) their coverage. While it is possible that some states or insurers may provide information about effectuation rates earlier, the first national data on ACA enrollments will likely come out in July 2026 with the Effectuated Enrollment Report, if the timing of past years is followed.

As shown in the chart below, the effectuation (or premium payment) rate has been quite high since 2022, meaning the vast majority of consumers who selected a plan ended up with coverage. For that reason, in recent years, plan selections and effectuated enrollment have often been discussed synonymously. However, the expiration of enhanced premium tax credits in 2026 will mark the first time that most ACA Marketplace enrollees experience a significant increase in their premium payments, making past years’ effectuation rates unreliable indicators of this year’s rate.

CMS typically releases an Effectuated Enrollment: Early Snapshot each summer. This data will provide a better picture of the impact of the expiration of enhanced tax credits on enrollment than plan selection data alone.

Based on past years, the Effectuated Enrollment: Early Snapshot report will likely be released in July 2026, and will report February 2026 effectuated enrollment, as measured on March 15, 2026. In other words, the July data release will likely show how many people had effectuated enrollment in February, based on what insurers know about premium payments by mid-March. However, as mentioned above, returning customers have until the end of March to make premium payments under the grace period. So even the data released in July of 2026 may still overstate the number of enrollees.

The effectuated enrollment data released in July of 2026 will likely not count new consumers who missed their binder payment for January or February, nor would it count consumers who were automatically renewed in December but then actively disenrolled in January. However, it wouldstill count people who were automatically renewed for January coverage and did not make a payment during the grace period—even if they eventually had their coverage retroactively terminated as of January 31.

The Effectuated Enrollment: Full Year 2026 data, likely to be released in the summer of 2027, would show the number of effectuated enrollees after all grace periods have elapsed. As a share of plan selections made during Open Enrollment, the chart below shows the final February effectuation rate from the Full Year (green) data has historically been a few percentage points lower than the Early Snapshot (blue).
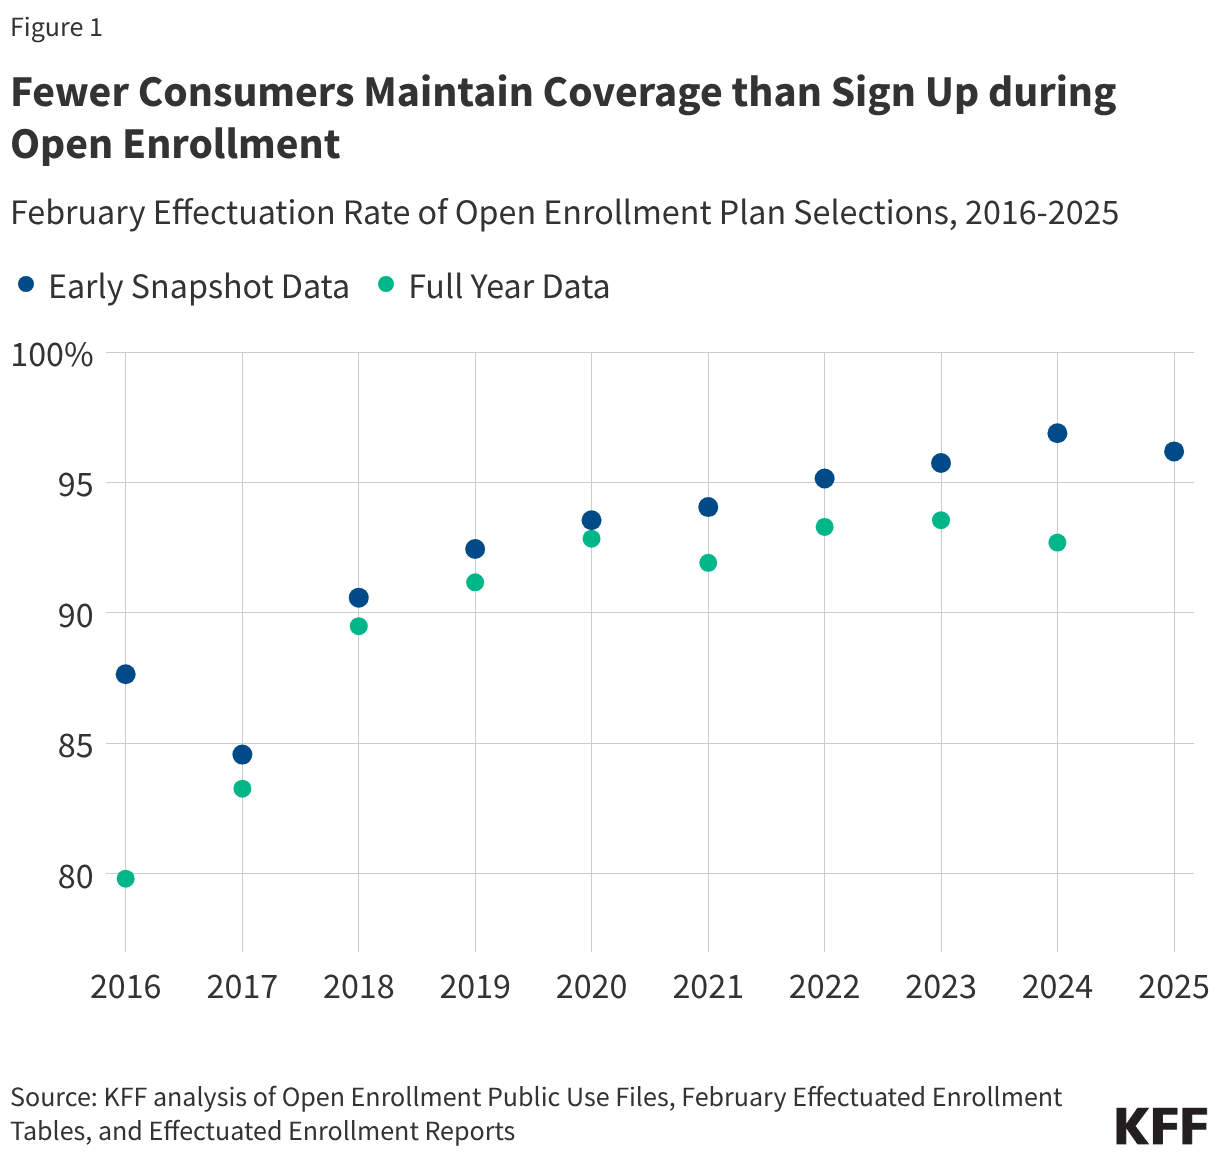
Fewer Consumers Maintain Coverage than Sign Up during Open Enrollment (Line chart)

Another reason the Effectuated Enrollment: Early Snapshot (expected to be released in July 2026) may not give a complete picture of the effect of expiring enhanced tax credits is that there could still be additional coverage loss later in the year. If an enrollee makes an initial premium payment but then decides their premium is unaffordable and drops their coverage mid-year, they may still be counted in the Effectuated Enrollment: Early Snapshot data even though they will not have coverage after their termination.

CMS may release additional effectuated enrollment counts before the Effectuated Enrollment: Full Year report; since this additional reporting may be after the run-out of grace periods, they would reflect finalized enrollment. In 2025, effectuated enrollment counts for the first five and seven months were released. Additionally, these releases may include information on the contribution of premium tax credits to the gross premium.

While effectuated enrollment data will tell us the number of people who are covered by ACA plans, it will not provide information about who paid their premium. The Open Enrollment Report and concurrent public use files, based on plan selections, will be the earliest source of information about income and other demographics of ACA enrollees. It is likely that the demographics and income distribution of ACA enrollees could shift from between the measurement of plan selections and effectuated enrollment. Additionally, the effectuated enrollment data from the Full Year report does not typically include metal level selection. There could be differences in payment rates for people who stay in their previous plan and face large premium increases and those who switch to lower-cost plans.

Quarterly Earnings Reports: April and May 2026

Prior to the publication of the effectuated enrollment data, some data on enrollment trends may be available from the insurers that enroll large shares of the individual market, during investor earnings calls. Insurers will host their fourth-quarter and year-end 2025 earnings calls in late January or February of 2026: Centene and Oscar will host their Q4 earnings calls on February 6 and February 10, respectively.

Insurers may start releasing membership counts for 2026 during their first-quarter 2026 earnings calls, expected to happen in April or May. Centene has announced their first-quarter earnings call for April 28. Elevance and UnitedHealthcare typically have first-quarter calls in April, while Oscar and Cigna typically report earnings in May. First-quarter calls that include enrollment information may not be fully adjusted for retroactive terminations due to nonpayment grace periods.

Insurer Rate Filings: Summer 2026

Every spring and summer, individual market insurers, including those offering ACA Marketplace plans, publicly file proposed premium rate changes to state regulators. These filings offer insight into what insurers believe is driving health cost growth and changes in enrollment. These rate filings will show insight into what insurers are planning in 2027 and may provide early counts of 2026 enrollment.

National Health Interview Survey Quarterly Releases: Likely January 2027

The National Health Interview Survey (NHIS) early release data will provide early indications of changes in the uninsured rate without the enhanced tax credits. From 2021-2024, first-quarter data came out in the summer of the same year, and data for the second quarter of the year came out closer to the end of the year. The Centers for Disease Control and Prevention has transitioned to biannual releases of data and released data for the first half of 2025 at the end of January 2026. If this release schedule remains consistent, data for the first half of 2026 may become available in early 2027.

Risk Adjustment Data: July 2027

Based on past years, the CMS Risk Adjustment Program State-Specific Data for 2026 is expected to come out in July 2027. The risk adjustment data will provide a state-by-state look at how many billable member months were reported for the ACA-compliant individual market. Because it will include on- and off-Marketplace enrollment, it will capture all people in ACA compliant coverage, even if they chose to purchase it off-exchange.

Issuer Level Enrollment Data: July 2027

The issuer-level enrollment data is split between HealthCare.gov and state-based exchanges. Data for HealthCare.gov states includes more information, including average monthly effectuated enrollment and average months of enrollment for those who have disenrolled. Additionally, issuer-level enrollment across all states will be made available through the Medical Loss Ratio Data and System Resources Public Use File, released late in the following year.

Enrollee-Level External Data Gathering Environment (EDGE): 2028

Enrollment by metal tier can be determined using the Enrollee-Level External Data Gathering Environment (EDGE) dataset, but this is subject to its own limitations: sparse enrollee demographic information, incomplete longitudinal data, and no information on terminated/non-effectuated coverage prevent fine-grained analysis on how the expiration of enhanced premium tax credits affected enrollee decisions. EDGE data for 2026 will likely not be available until 2028.
FY 2026 National Security, Department of State and Related Programs (NSRP) Global Health Funding in the Consolidated Appropriations Act

Published: Feb 4, 2026

Update: On February 3, 2026, the President signed the “Consolidated Appropriations Act, 2026” which includes funding provided in the FY 2026 National Security, Department of State and Related Programs (NSRP) appropriations bill and accompanying explanatory statement detailed below. This resource was originally published on January 14, 2026.

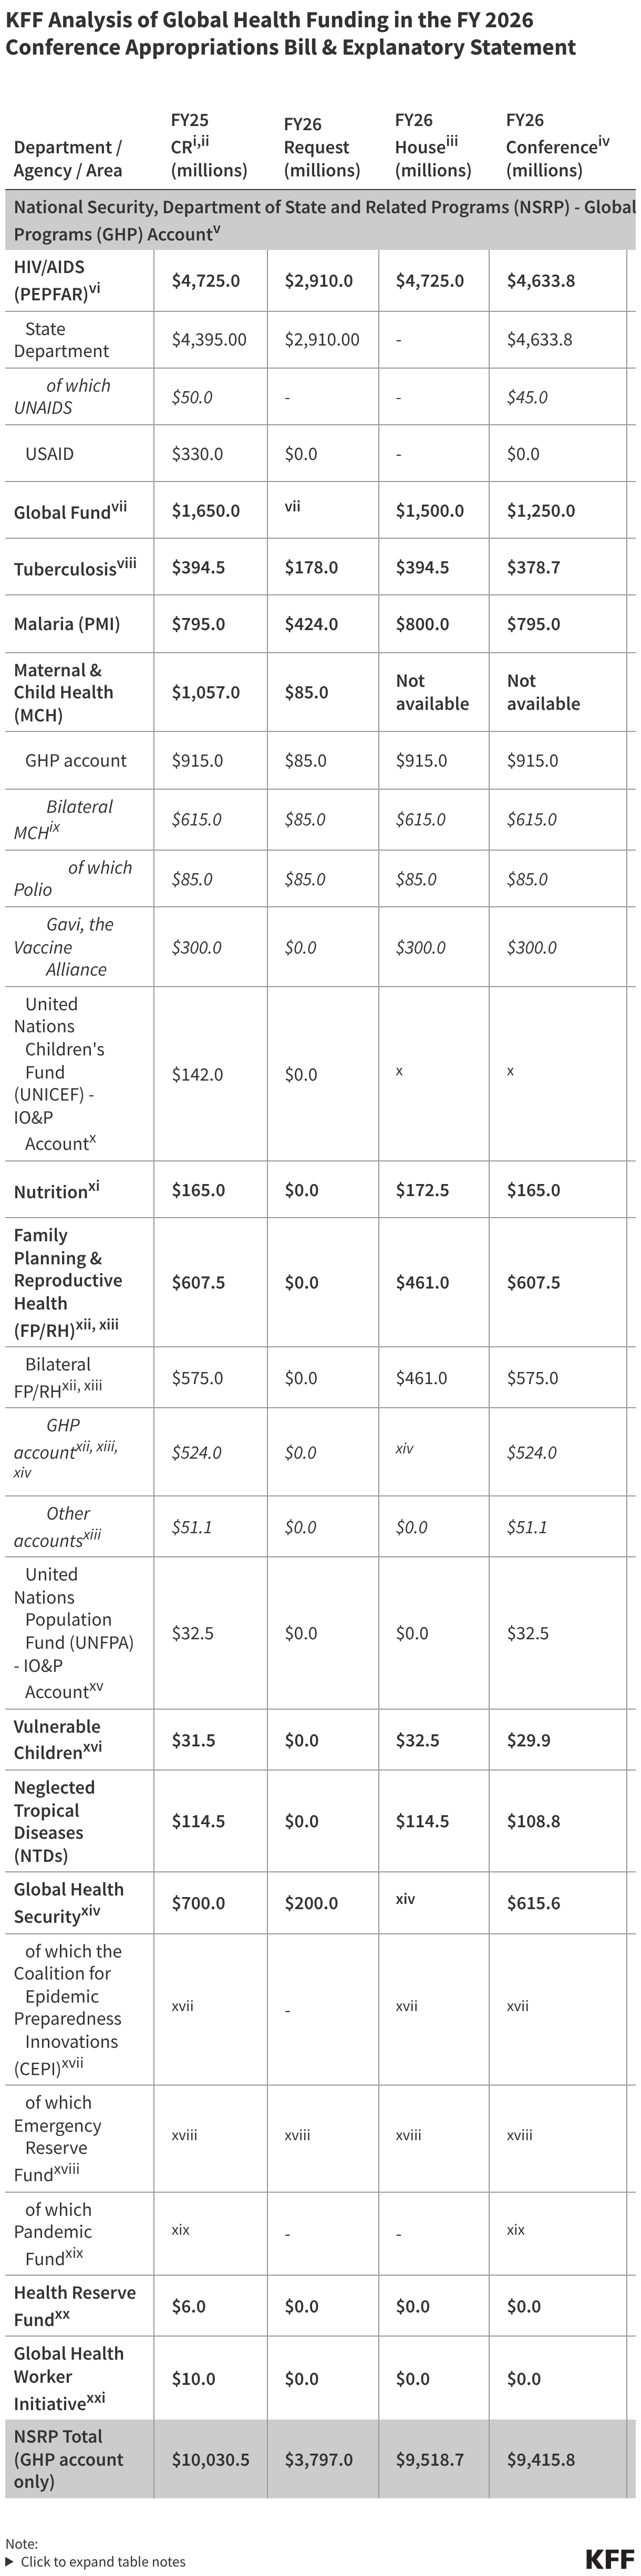
On January 11, 2026, the Appropriations Committee released the FY 2026 National Security, Department of State and Related Programs (NSRP) (formerly State, Foreign Operations, and Related Programs [SFOPs]) appropriations bill and accompanying explanatory statement. The bill and explanatory statement include funding for U.S. global health programs at the State Department. Funding for global health programs at the State Department through the Global Health Programs (GHP) account, which represents the bulk of global health assistance, totals $9.4 billion, which is a decrease of $615 million (-6%) compared to the FY25 level ($10 billion). All program areas either decreased or remained flat as follows:

  • Decreased: Funding for the Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund), bilateral HIV, tuberculosis (TB), global health security, neglected tropical diseases (NTDs), and vulnerable children declined; while the Global Fund accounted for the largest decrease (-$400 million or -24%), this funding supports the administration’s pledge of $4.6 billion for the eighth replenishment and serves as the first installment of that pledge. In addition, the explanatory statement accompanying the bill states that there are also “sufficient unobligated balances” from prior Acts “to fulfill the United States pledge for the seventh replenishment.”
  • Remained Flat: Funding for malaria, maternal and child health (MCH), nutrition, and family planning and reproductive health (FP/RH) remained flat.

In addition, the bill included provisions that either impact or provide direction on global health funding including:

  • Program Area Amounts: Funding for many of the global health program areas is specified in the explanatory statement (rather than the bill). Unlike prior years, this bill specifically states that funding “shall be made available at not less than the amounts specifically designated in the respective tables included in the explanatory statement” ensuring that the administration is required to provide the amounts for the areas specified. The bill also prohibits the administration from deviating from the global health amounts in the bill and explanatory statement.
  • Funding Availability Timeframe: PEPFAR funding (bilateral HIV and the contribution to the Global Fund) is available for five years. Funding for most other program areas is provided for two years, with the exception of funding for Gavi, the Vaccine Alliance and the Coalition for Epidemic Preparedness Innovations (CEPI), which is provided for one year.
  • Reports/Briefings: The bill requires the administration to provide updates (via reports or briefings) on numerous global health areas including (but not limited to) the PEPFAR Transition Strategy, Market Access Strategy, bilateral health agreements, multilateral health engagement, the development of an Innovation Fund, and the status of available funding (i.e. apportionment, allocations, obligations, and disbursements).
  • Additional Requirements: The bill requires coordination with the Centers for Disease Control and Prevention (CDC) on global health activities and establishes the Prevention, Treatment, and Response Initiative, which supports “research, development, and delivery of vaccines and other prevention technologies”.

See the table below for additional detail on global health funding. See other budget summaries (including the summary on FY 2026 Labor, Health and Human Services, Education, and Related Agencies (Labor HHS) global health funding) and the KFF budget tracker for details on historical annual appropriations for global health programs.

KFF Analysis of Global Health Funding in the FY 2026 Conference Appropriations Bill & Explanatory Statement (Table)

FY 2026 Labor, Health and Human Services, Education, and Related Agencies (Labor HHS) Global Health Funding in the Consolidated Appropriations Act

Published: Feb 4, 2026

Update: On February 3, 2026, the President signed the “Consolidated Appropriations Act, 2026” which includes funding provided in the FY 2026 Labor, Health and Human Services, Education, and Related Agencies (Labor HHS) conference bill and accompanying report detailed below. This resource was originally published on January 22, 2026.

The Committee on Appropriations released its FY 2026 Labor, Health and Human Services, Education, and Related Agencies (Labor HHS) conference bill and accompanying report on January 20, 2026.

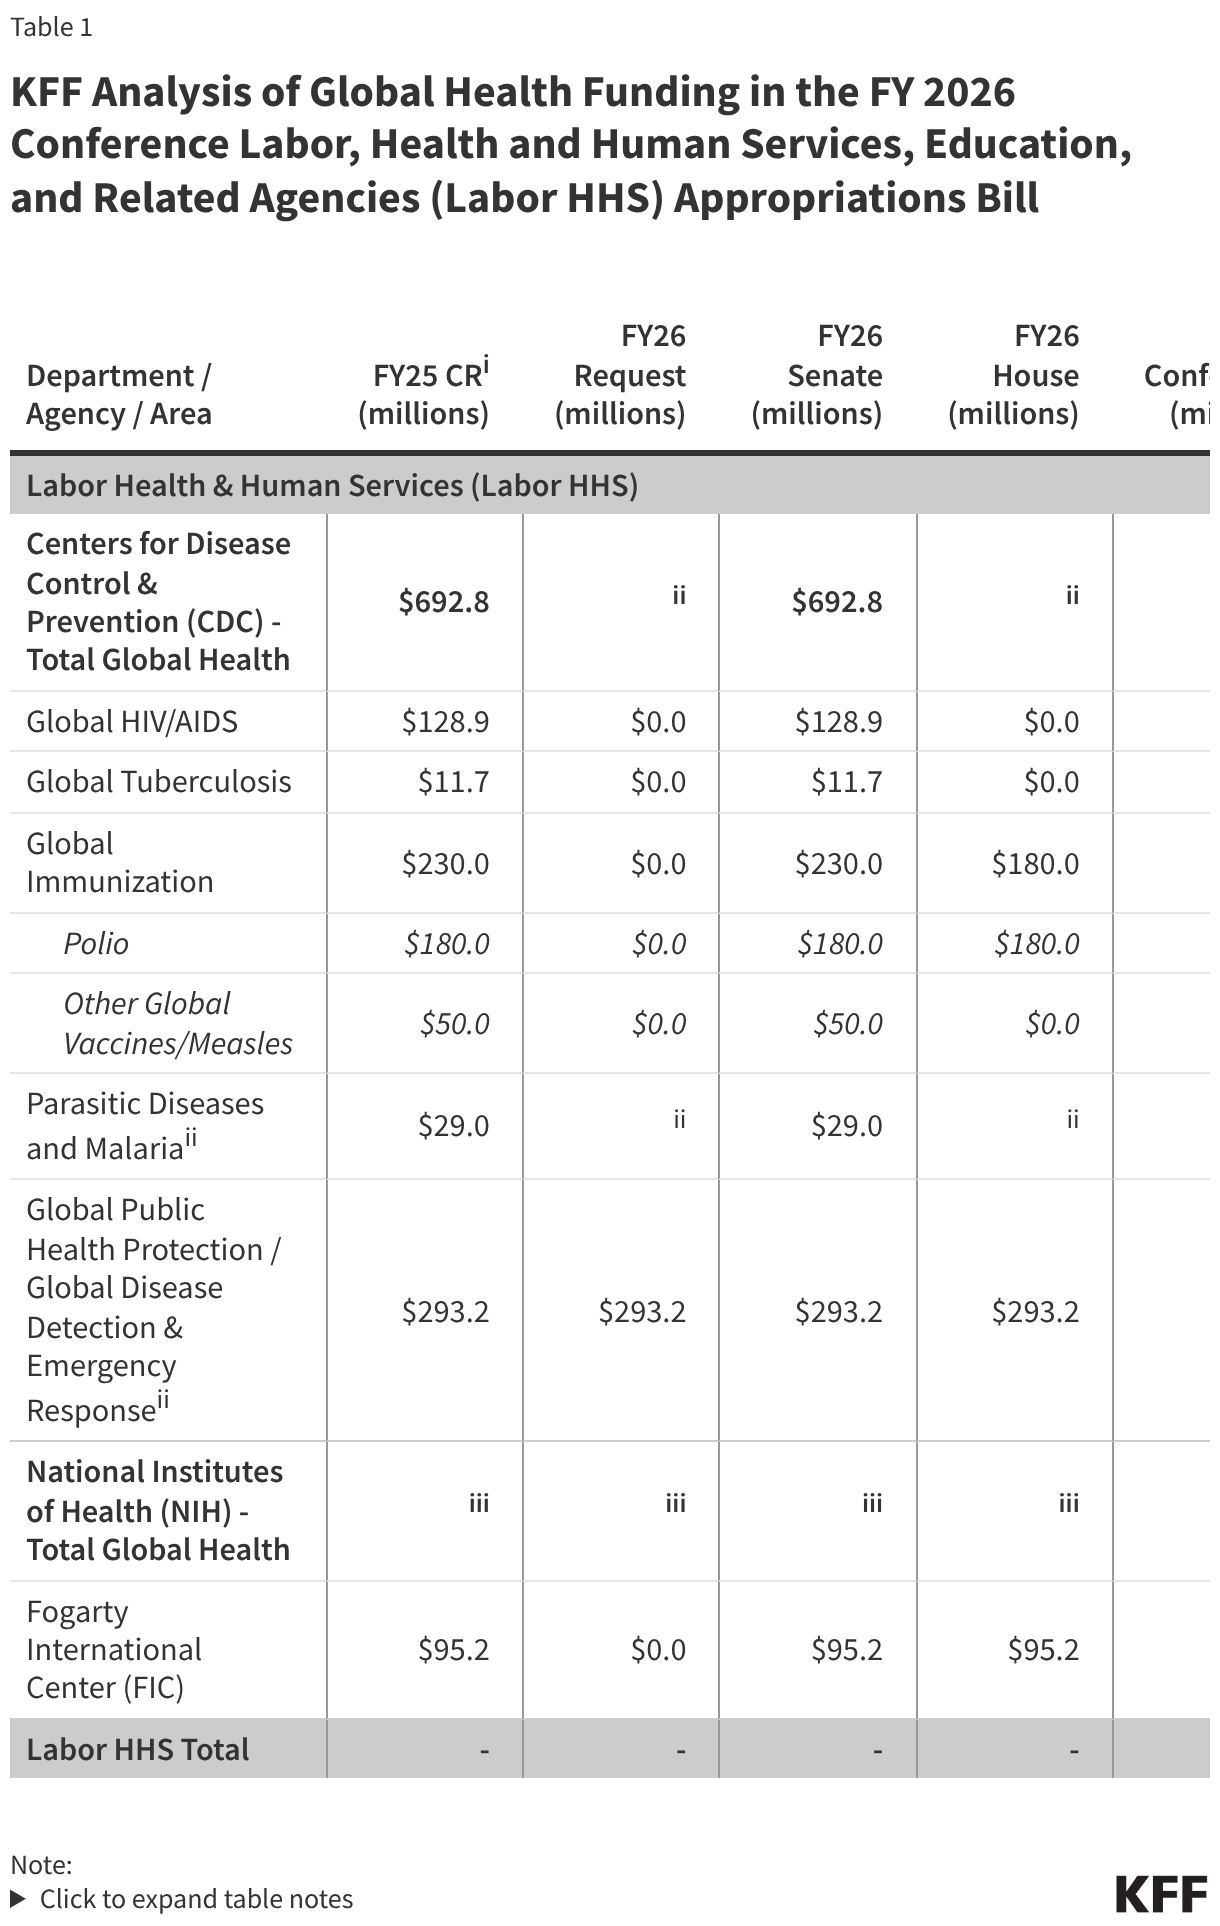
While most U.S. global health funding is provided to the State Department through a separate appropriations bill (see the KFF budget summary on this funding here), the Labor HHS appropriations bill includes funding for global health programs at the Centers for Disease Control and Prevention (CDC) as well as funding for global health research activities at the National Institutes of Health (NIH). Total global health funding at CDC and NIH through the Labor HHS bill is not yet known, as funding for some programs (i.e. global HIV/AIDS and malaria research) at NIH is determined at the agency level rather than specified by Congress in annual appropriations bills. Funding for global health in the Labor HHS bill remained flat compared to the FY 20251 level as follows:

  • CDC: Funding for global health programs at CDC totals $693 million, the same level as the FY 2025 enacted amount.2 Within CDC, funding for each specific global health program area was also maintained at the FY 2025 level.
  • NIH: Funding for global health research activities at the Fogarty International Center (FIC) at NIH totals $95 million, the same level as the FY 2025 enacted amount.

In addition, Section 236 under the Labor HHS section of the bill specifically states that funding “shall be for the budget activities, and in the amounts specified in the table under each such heading in the explanatory statement” instructing the administration to provide the amounts for the areas specified.

See the table below for additional details on global health funding. See other budget summaries and the KFF budget tracker for details on historical annual appropriations for global health programs.

KFF Analysis of Global Health Funding in the FY 2026 Conference Labor, Health and Human Services, Education, and Related Agencies (Labor HHS) Appropriations Bill (Table)

  1. Funding for FY25 was provided in a full-year Continuing Resolution (CR), which maintained FY24 levels. All FY25 amounts and associated notes are based on those specified in relevant FY24 appropriations bills. ↩︎
  2. The FY26 Request eliminates CDC's Global Health Center and most of its bilateral programs, except funding for "Global Disease Detection & Emergency Response", which is transferred to "Crosscutting Activities and Program Support", and "Parasitic Diseases and Malaria", which is transferred to "Emerging and Zoonotic Infectious Diseases". ↩︎
News Release

Poll: People View Prior Authorization as Greatest Burden in Navigating the Health System

Many Report Impact on their Care, Finances and Well-being

Published: Feb 2, 2026

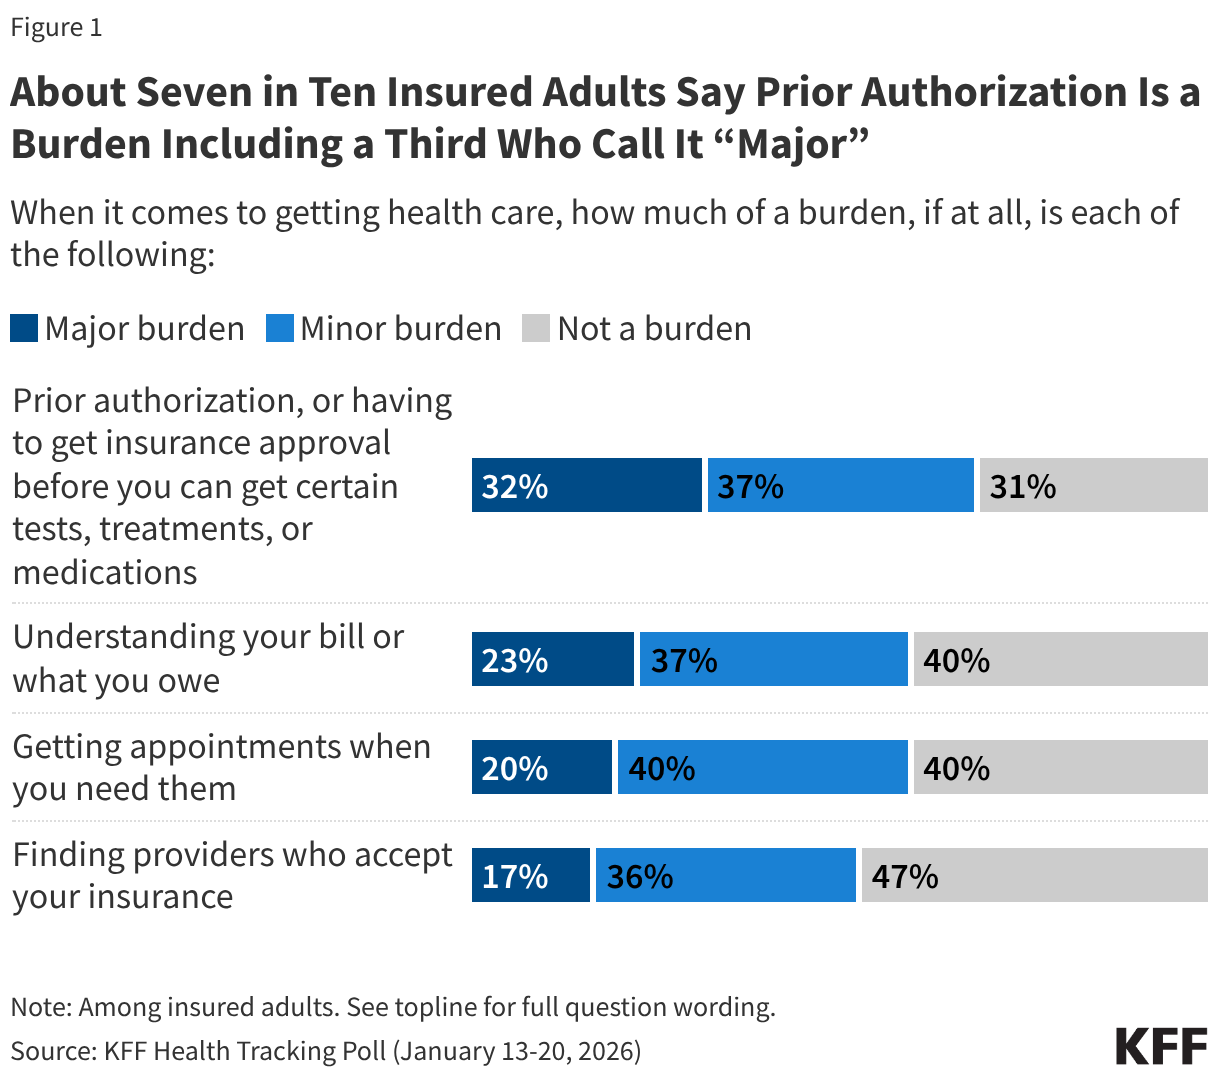
New KFF polling explores the challenges beyond costs that people with insurance face in navigating the health care system. People cite prior authorization review as their top problem by a wide margin, with a third (32%) saying prior authorization requirements are a “major burden.”

That’s more than say the same about understanding their bill or what they owe (23% say it is a major burden), getting appointments when they need them (20%), or finding providers who accept their insurance (17%).

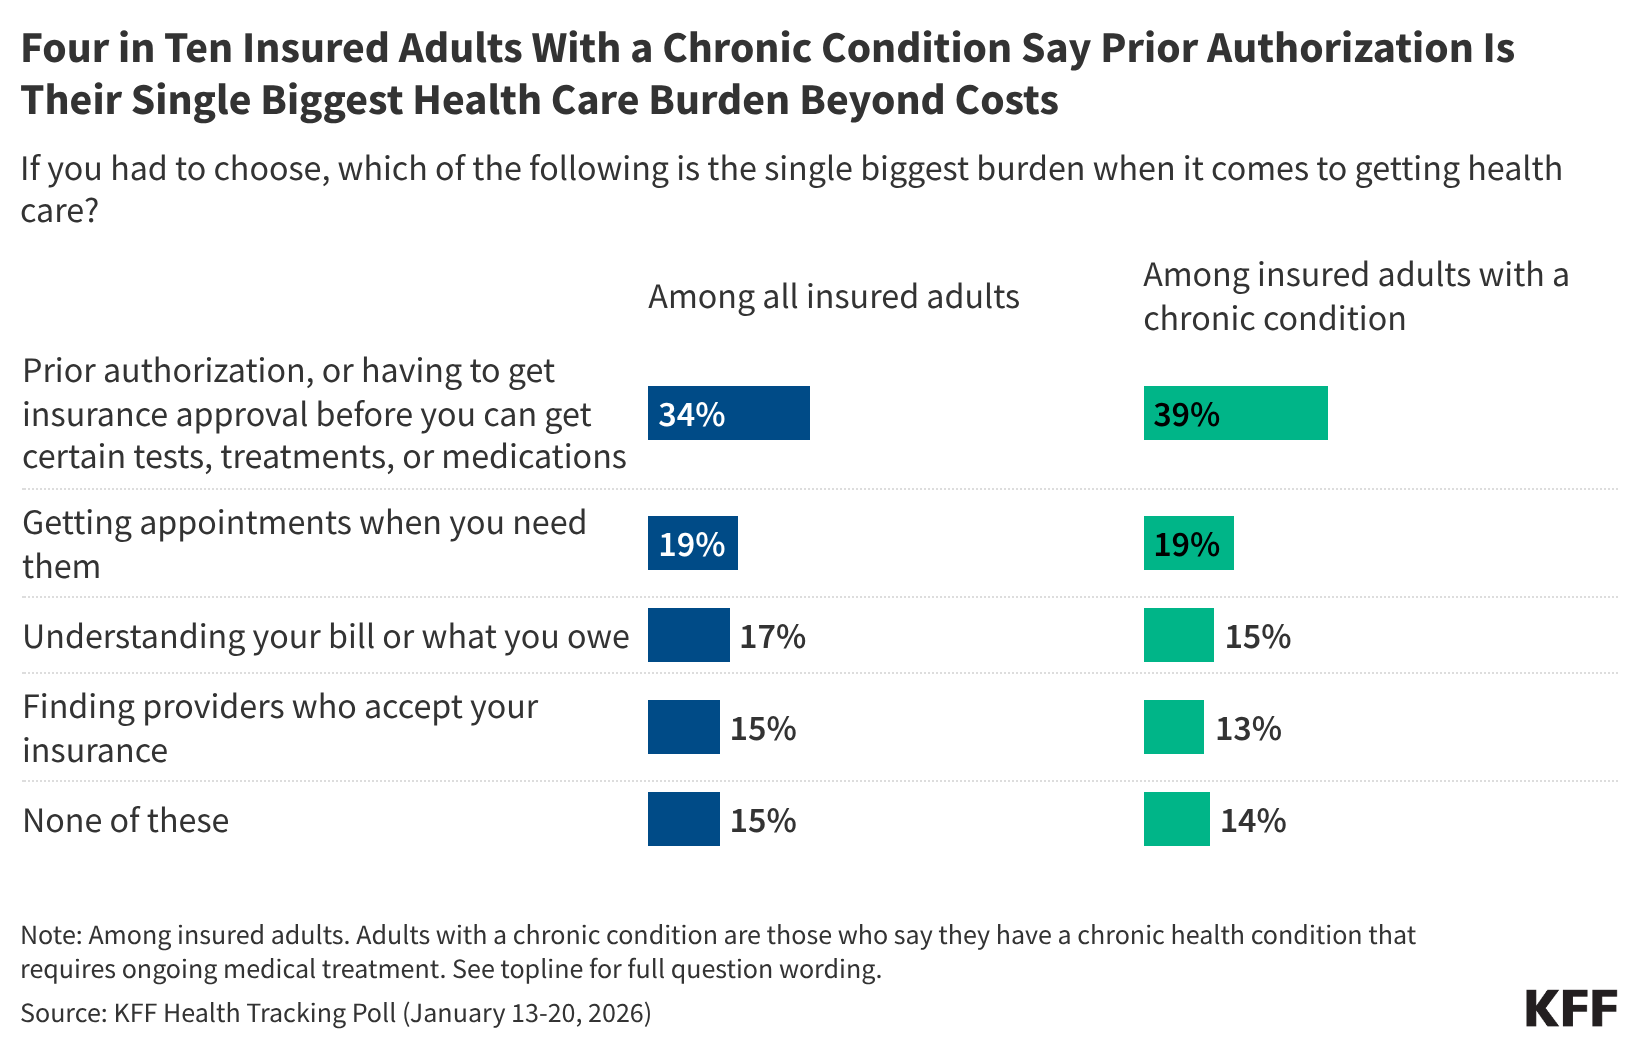
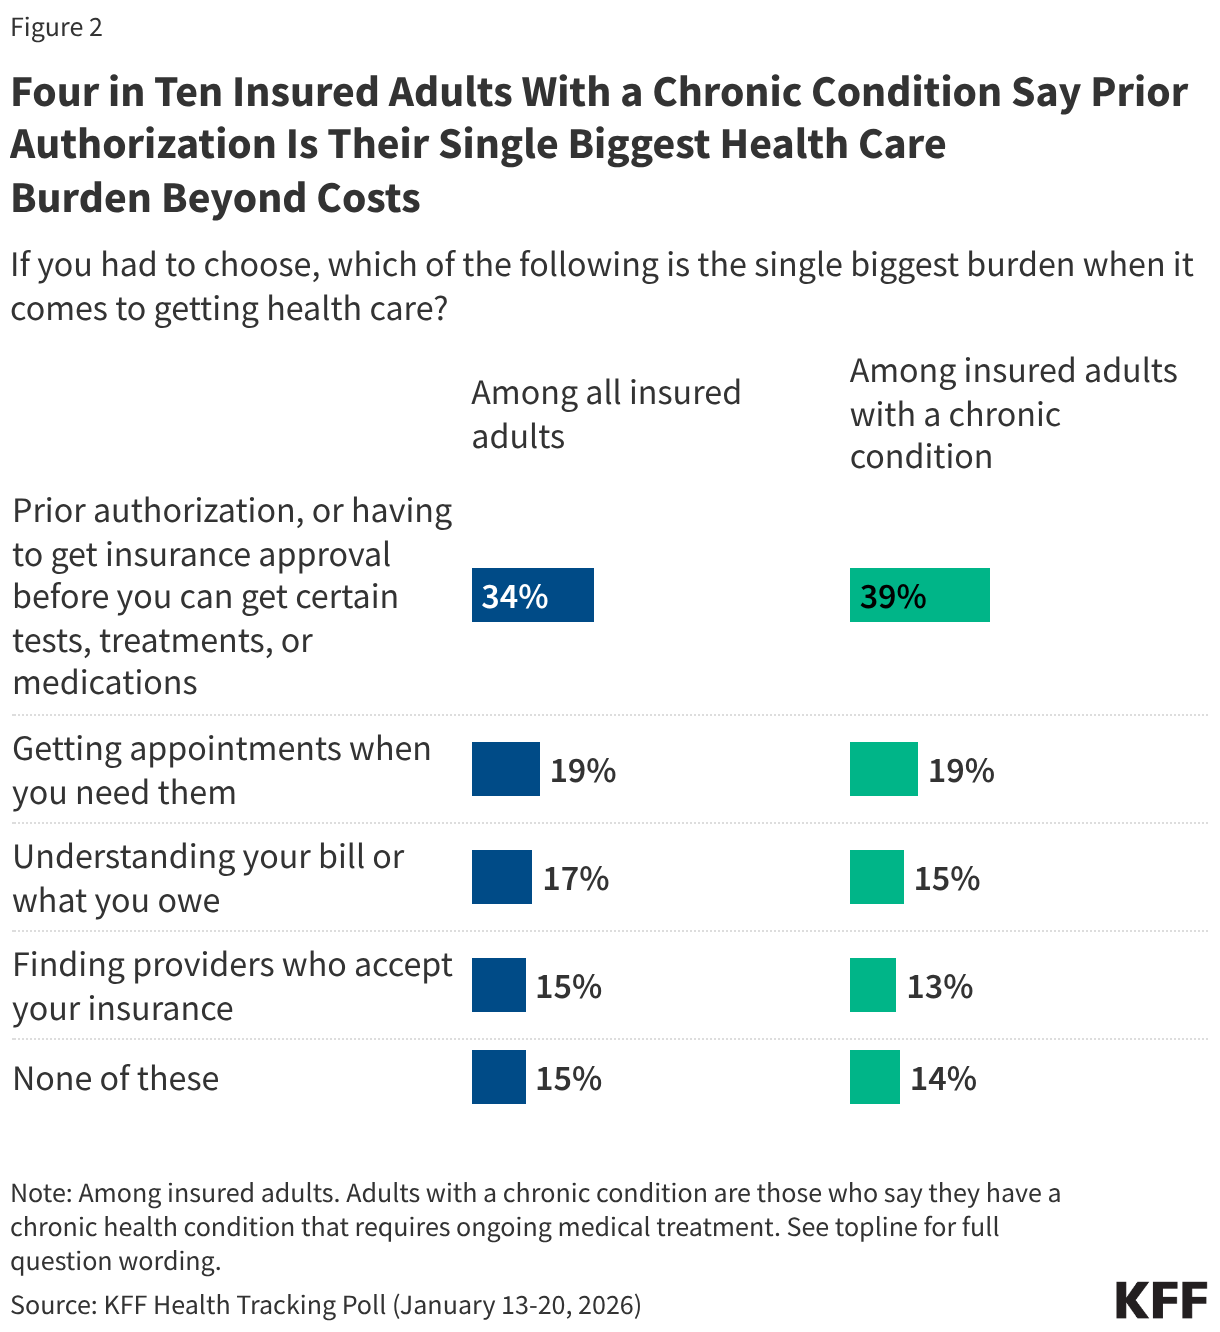
When asked to choose which of those four factors is “the single biggest burden,” prior authorization before accessing certain tests, treatments, or medication ranks at the top (34%). Among people with a chronic condition that requires ongoing medical treatment (about half of all insured adults), 4 in 10 (39%) say prior authorization is the single biggest burden when it comes to getting care, more than twice the share who say the same about other obstacles.

“The complexity of the health system drives patients crazy, can have real consequences, and disproportionately affects people who are sick,” KFF President and CEO Drew Altman said. “Prior authorization review is the poster child for that complexity.”

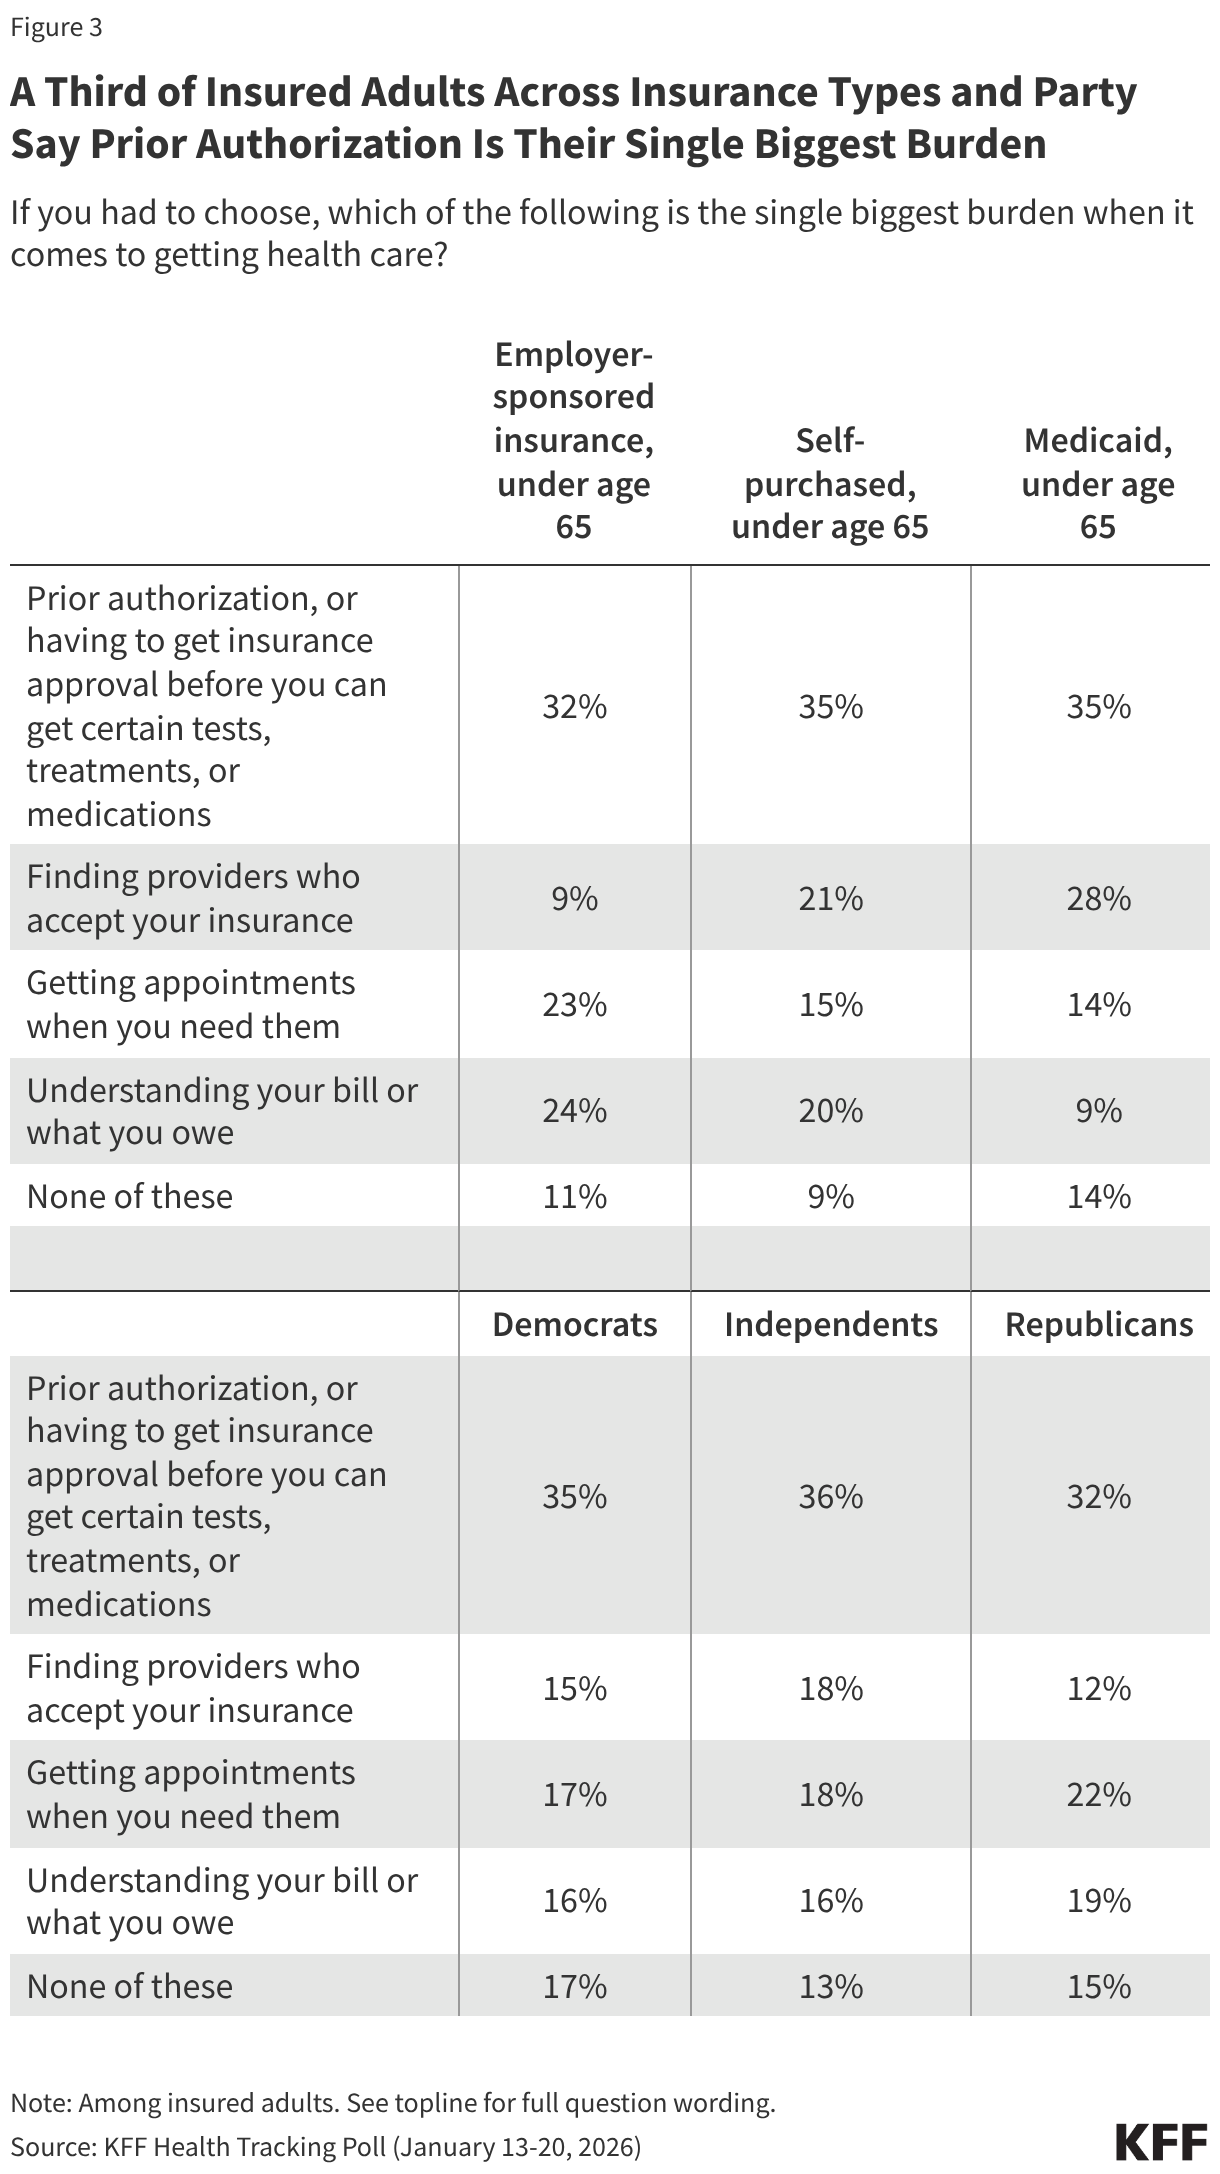
Prior authorization ranks as the single biggest burden for people with employer coverage and Medicaid, as well as those who buy their own coverage (largely through the Affordable Care Act’s Marketplaces).

During the prior authorization process, some treatments or medications recommended by a provider may be delayed and, in some instances, an insurance company may end up denying medication or treatment.

About half (47%) of insured adults – and a larger share (57%) of those with chronic conditions – say their access to a certain health care service, treatment, or medication has been denied, delayed, or altered in the past two years by their health insurer.

Among those who report such denials, delays, or alterations, about a third say it had a “major negative impact” on their mental health and emotional well-being (34%) and finances (33%), and a quarter say it had a “major negative impact” on their physical health (26%). This translates to about 1 in 5 of all adults with insurance saying that their mental or physical health, or finances, have been majorly impacted.

Designed and analyzed by public opinion researchers at KFF, this survey was conducted January 13-20, 2026, online and by telephone among a nationally representative sample of 1,426 U.S. adults in English and in Spanish. The margin of sampling error is plus or minus 3 percentage points for the full sample. For results based on other subgroups, the margin of sampling error may be higher.

Poll Finding

KFF Health Tracking Poll: Prior Authorizations Rank as Public’s Biggest Burden When Getting Health Care

Published: Feb 2, 2026

As the latest KFF Health Tracking Poll shows, affordability is the public’s biggest concern, with the cost of health care ranking as their top economic worry. However, KFF polls have demonstrated that beyond costs, insured people report a whole host of issues navigating the health care system. This report looks at which aspects of accessing care and health insurance are the biggest problem for insured adults and finds that prior authorizations – or the process of having to get insurance approval before accessing certain tests, treatments, or medications – are having an outsized impact on insured adults.

One in three insured adults in the U.S. say they find prior authorizations a “major burden” to getting health care. An additional four in ten (37%) say the process is a “minor burden,” bringing the total share of insured adults who find the process burdensome to about seven in ten (69%). This is larger than the share who say other aspects are burdensome such as understanding bills or what is owed (60%), getting needed appointments (60%), or finding providers who accept their insurance (53%).

Stacked bar chart showing how much of a burden insured adults believe certain aspects of getting health care are.

When asked to choose which aspect of getting health care, beyond costs, is the single biggest burden, one in three insured adults (34%) choose prior authorizations, followed by getting needed appointments (19%), understanding their bill (17%), or finding providers who accept their insurance (15%). The choice of prior authorizations as the single biggest burden is even more stark among adults with a chronic condition that requires ongoing medical treatment (about half of all adults). These individuals often require more treatments and medications, resulting in more interactions with health insurance companies and health care providers. Four in ten (39%) insured adults with a chronic condition say prior authorizations are the single biggest burden when it comes to getting health care, at least twice the share who say the same about the other aspects of health care asked about.

Split bar chart showing how much of a burden insured adults and insured adults with a chronic condition believe certain aspects of getting health care are.

Prior authorizations are also identified as the single biggest burden for insured adults across partisans, as well as among individuals across insurance types that typically require prior authorizations such as individuals with Medicaid, people who buy their own health insurance, and people who get health insurance through an employer. Notably, about three in ten (28%) Medicaid enrollees identify finding providers who accept their insurance as the biggest burden, but small shares identify other issues as their biggest burden.1

A table showing the single biggest health care burden named by insured adults, broken out by insurance type and by party identification.

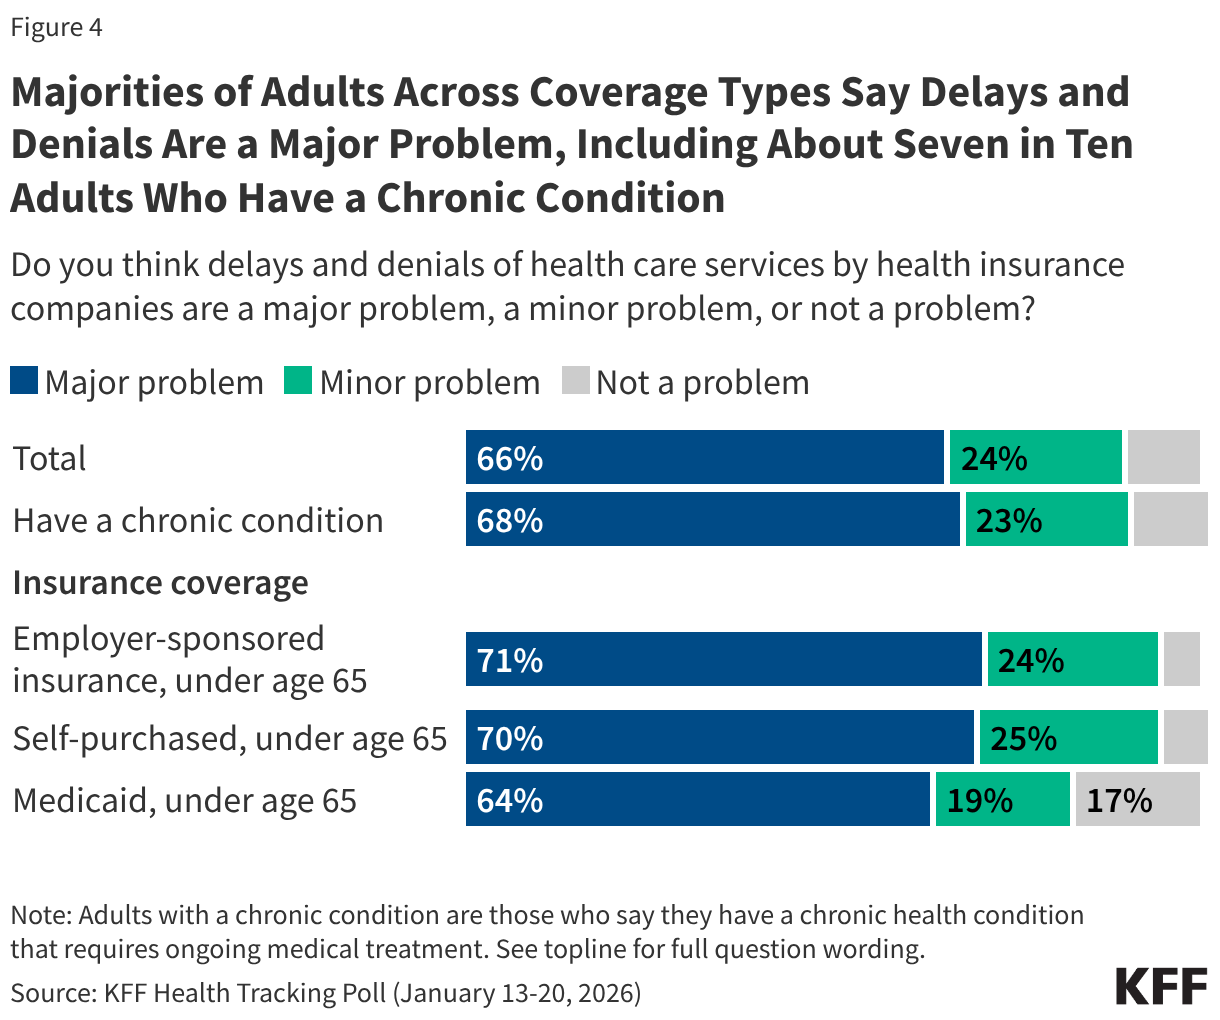
During the prior authorization process, some treatments or medications recommended by a provider may be delayed and, in some instances, an insurance company may end up denying medication or treatment. Overall, about two-thirds of adults say delays and denials of health care services by health insurance companies are a “major problem” with an additional one in four (24%) who say they are a “minor problem.” Just one in ten adults say delays and denials of services by insurance companies are not a problem in our current health care system.  More than six in ten across Medicaid enrollees, self-purchasers, and those with employer coverage say the delays and denials of care by insurance companies are a “major problem.”

A stacked bar chart showing how much of a problem adults view delays and denials of health care services by insurance companies.

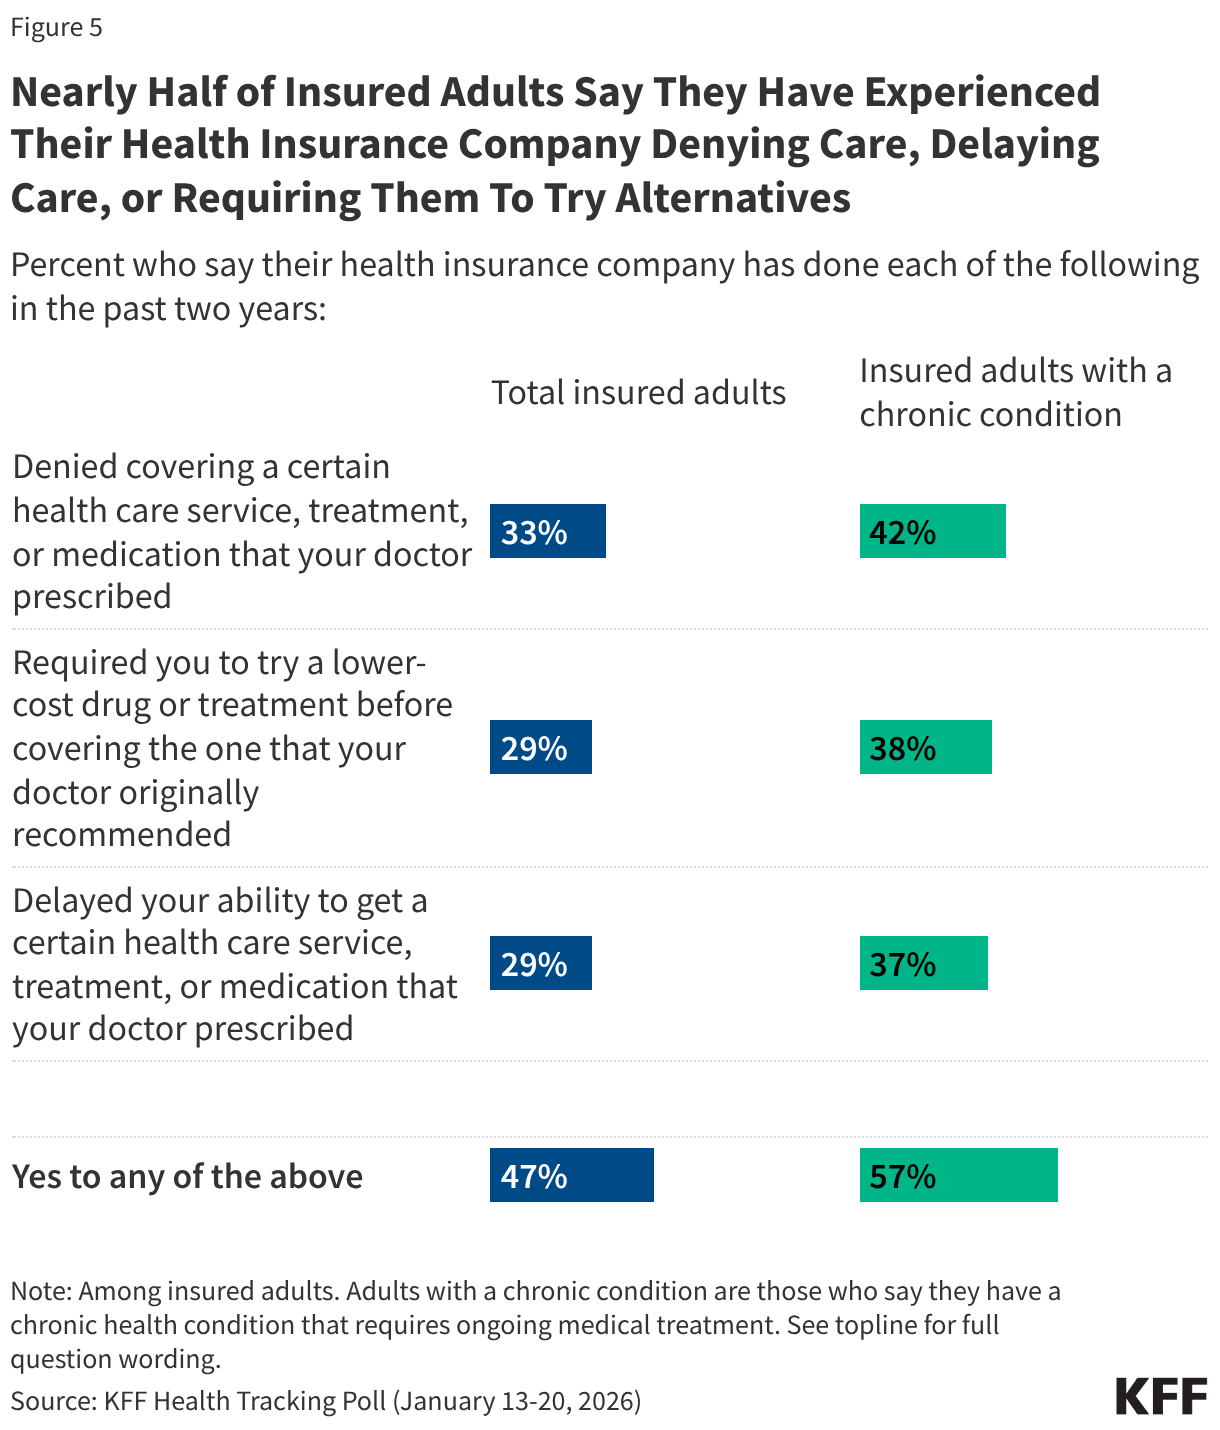
About one in three insured adults (33%) say they have had a health insurance company deny coverage for a certain health care service treatment, or medication prescribed by their doctor in the past two years. Three in ten insured adults say that a health insurance company has delayed their ability to get such services, treatments, or medications (29%) or required them to try a lower-cost drug or treatment before covering the one that was originally recommended by their provider (29%). These issues are even more common among insured adults with a chronic condition with about four in ten reporting that an insurance company has required them to try a lower-cost drug or treatment (38%), deny coverage for a certain service or medication (42%), or delayed their ability to get prescribed care (37%). Overall, nearly half (47%) of insured adults say they have had a certain service, treatment, or medication either denied or delayed in the past two years, rising to nearly six in ten (57%) among those with a chronic condition.

Split bar chart showing the share of insured adults and insured adults with a chronic condition who say they've experienced issues with their health insurance company.

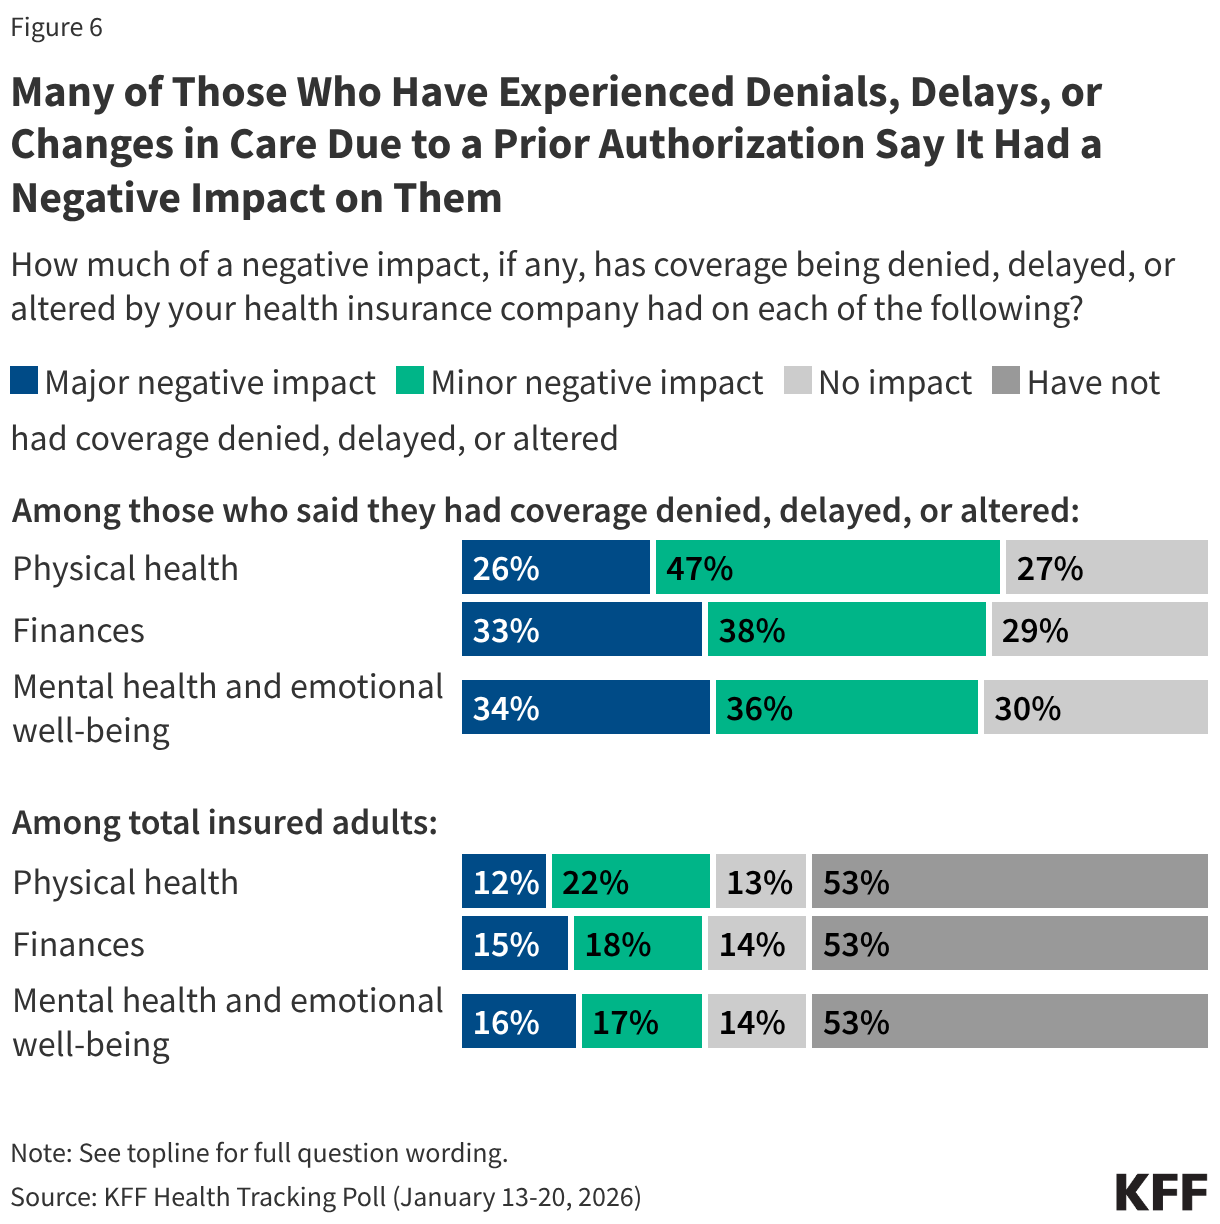
Denial and delays by health insurance companies can lead to negative consequences for people’s physical, mental, and financial health. One in three of those who experienced a denial or delay say the actions required by their health insurance company had a “major negative impact” on their mental health and emotional well-being as well as on their finances (about one in six of all insured adults).  One in four (one in eight of all insured adults) say the delays or denials has a “major negative impact” on their physical health.

A stacked bar chart showing how much of an impact issues with prior authorizations have had on insured adults, broken out by those who said they had previous experience with this and among total insured adults.


  1. Prior authorization is more common in Medicare Advantage than Traditional Medicare. Because this analysis is unable to break out individuals with traditional Medicare versus Medicare Advantage, we do not include Medicare as a subgroup in our analysis. These individuals are included in both the total group and the group with chronic conditions.  To learn more about prior authorizations for Medicare, more available at https://www.kff.org/medicare/medicare-advantage-insurers-made-nearly-53-million-prior-authorization-determinations-in-2024/. ↩︎

This KFF Health Tracking Poll/KFF Tracking Poll on Health Information and Trust was designed and analyzed by public opinion researchers at KFF. The survey was conducted January 13-20, 2026, online and by telephone among a nationally representative sample of 1,426 U.S. adults in English (n=1,355) and in Spanish (n=71). The sample includes 1,028 adults (n=60 in Spanish) reached through the SSRS Opinion Panel either online (n= 1,003) or over the phone (n=25). The SSRS Opinion Panel is a nationally representative probability-based panel where panel members are recruited randomly in one of two ways: (a) Through invitations mailed to respondents randomly sampled from an Address-Based Sample (ABS) provided by Marketing Systems Groups (MSG) through the U.S. Postal Service’s Computerized Delivery Sequence (CDS); (b) from a dual-frame random digit dial (RDD) sample provided by MSG. For the online panel component, invitations were sent to panel members by email followed by up to three reminder emails. 

Another 398 (n=11 in Spanish) adults were reached through random digit dial telephone sample of prepaid cell phone numbers obtained through MSG. Phone numbers used for the prepaid cell phone component were randomly generated from a cell phone sampling frame with disproportionate stratification aimed at reaching Hispanic and non-Hispanic Black respondents. Stratification was based on incidence of the race/ethnicity groups within each frame. Among this prepaid cell phone component, 149 were interviewed by phone and 249 were invited to the web survey via short message service (SMS). 

Respondents in the prepaid cell phone sample who were interviewed by phone received a $15 incentive via a check received by mail or an electronic gift card incentive. Respondents in the prepaid cell phone sample reached via SMS received a $10 electronic gift card incentive. SSRS Opinion Panel respondents received a $5 electronic gift card incentive (some harder-to-reach groups received a $10 electronic gift card). In order to ensure data quality, cases were removed if they failed two or more quality checks: (1) attention check questions in the online version of the questionnaire, (2) had over 30% item non-response, or (3) had a length less than one quarter of the mean length by mode. Based on this criterion, 2 cases was removed. 

The combined cell phone and panel samples were weighted to match the sample’s demographics to the national U.S. adult population using data from the Census Bureau’s 2025 Current Population Survey (CPS), September 2023 Volunteering and Civic Life Supplement data from the CPS, and the 2025 KFF Benchmarking Survey with ABS and prepaid cell phone samples. The demographic variables included in weighting for the general population sample are gender, age, education, race/ethnicity, region, civic engagement, frequency of internet use and political party identification. The weights account for differences in the probability of selection for each sample type (prepaid cell phone and panel). This includes adjustment for the sample design and geographic stratification of the cell phone sample, within household probability of selection, and the design of the panel-recruitment procedure. 

The margin of sampling error including the design effect for the full sample is plus or minus 3 percentage points. Numbers of respondents and margins of sampling error for key subgroups are shown in the table below. For results based on other subgroups, the margin of sampling error may be higher. Sample sizes and margins of sampling error for other subgroups are available on request. Sampling error is only one of many potential sources of error and there may be other unmeasured error in this or any other public opinion poll. KFF public opinion and survey research is a charter member of the Transparency Initiative of the American Association for Public Opinion Research. 

GroupN (unweighted)M.O.S.E.
Total1,426± 3 percentage points
 
Party ID
Democrats473± 6 percentage points
Independents483± 6 percentage points
Republicans367± 6 percentage points
  
MAGA Republicans/Rep leaners352± 6 percentage points
MAHA supporters618± 5 percentage points
Parents or guardians of children under 18 living in their household436± 6 percentage points
Poll Finding

5 Charts About Public Opinion on the Affordable Care Act

Published: Jan 30, 2026

Note: This resource was originally posted on February 22, 2024, and was most recently updated January 30, 2026, to include newer polling data on the public’s views of the ACA.

#1: Attitudes Toward the ACA Continue to Be More Favorable than Unfavorable, Divided Among Partisans

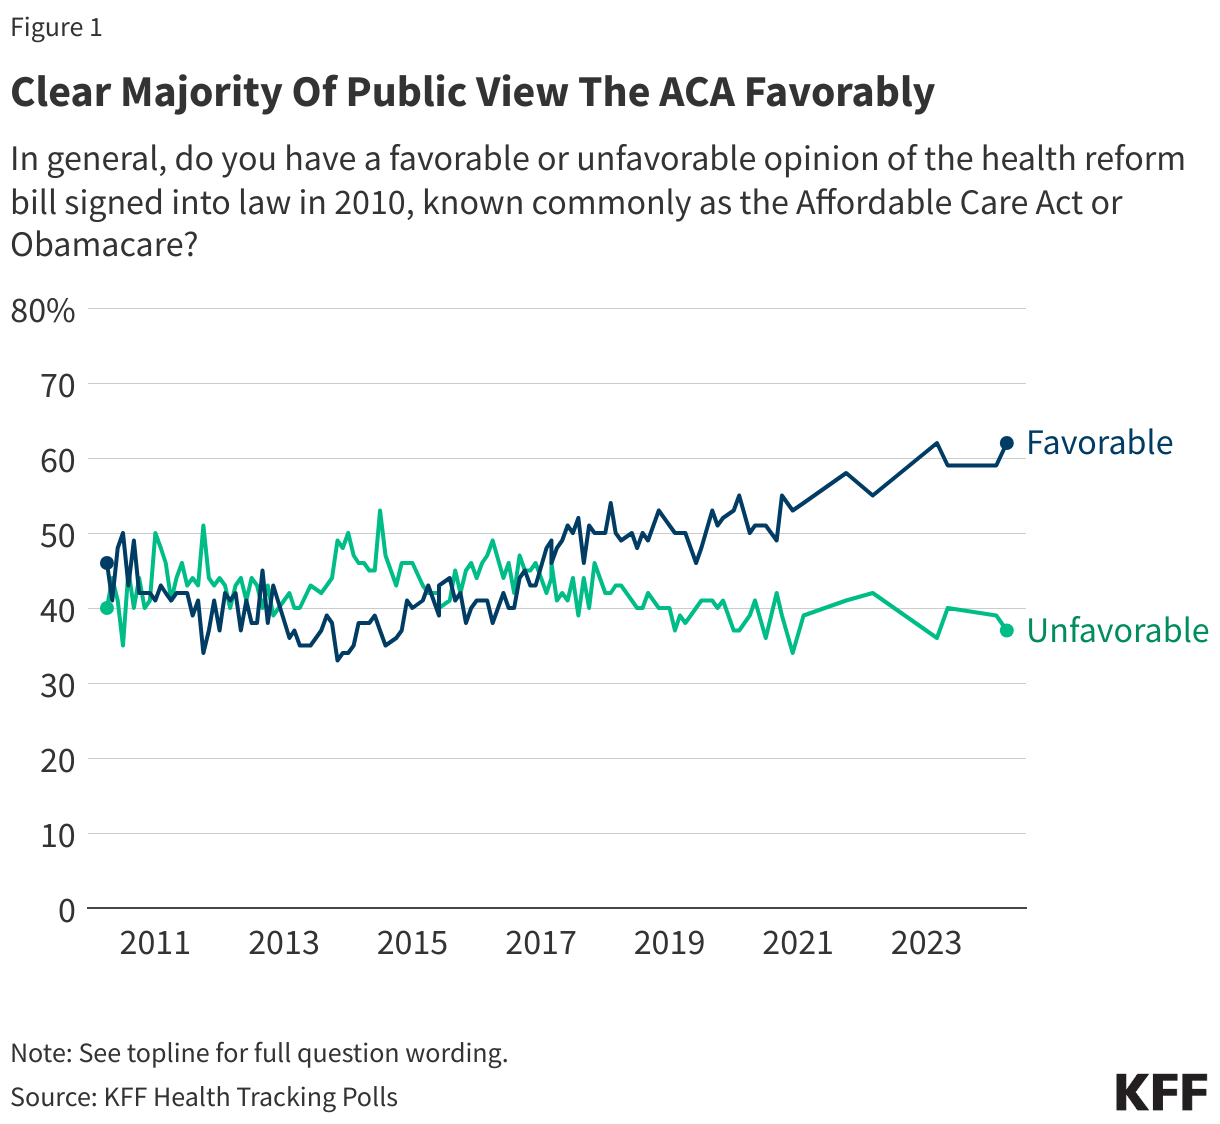
Public opinion of the Affordable Care Act (ACA) has been largely divided along partisan lines since the law was passed in 2010. Following Republican efforts to repeal the ACA in the summer of 2017, KFF Health Tracking Polls show an uptick in overall favorability towards the law, and since then, a larger share has held a favorable than an unfavorable view. In early 2026, about six in ten adults (58%) say they hold a favorable opinion of the ACA while about four in ten (41%) hold a negative opinion of the law. Views of the ACA are still largely driven by partisanship; about nine in ten Democrats (91%) along with six in ten independents (62%) view the law favorably, while about three-fourths of Republicans (77%) hold unfavorable views. Explore more demographic breakdowns using KFF’s interactive: The Public’s Views on the ACA.

Line chart showing percent of adults over time who say they have a favorable or an unfavorable opinion of the Affordable Care Act. Results shown from April 2010 to February 2024.

The ACA has been the subject of both legal challenges and Congressional actions aimed at overturning the 2010 health care law. However, many of the specific provisions included in the law are popular and the public would like them to remain.

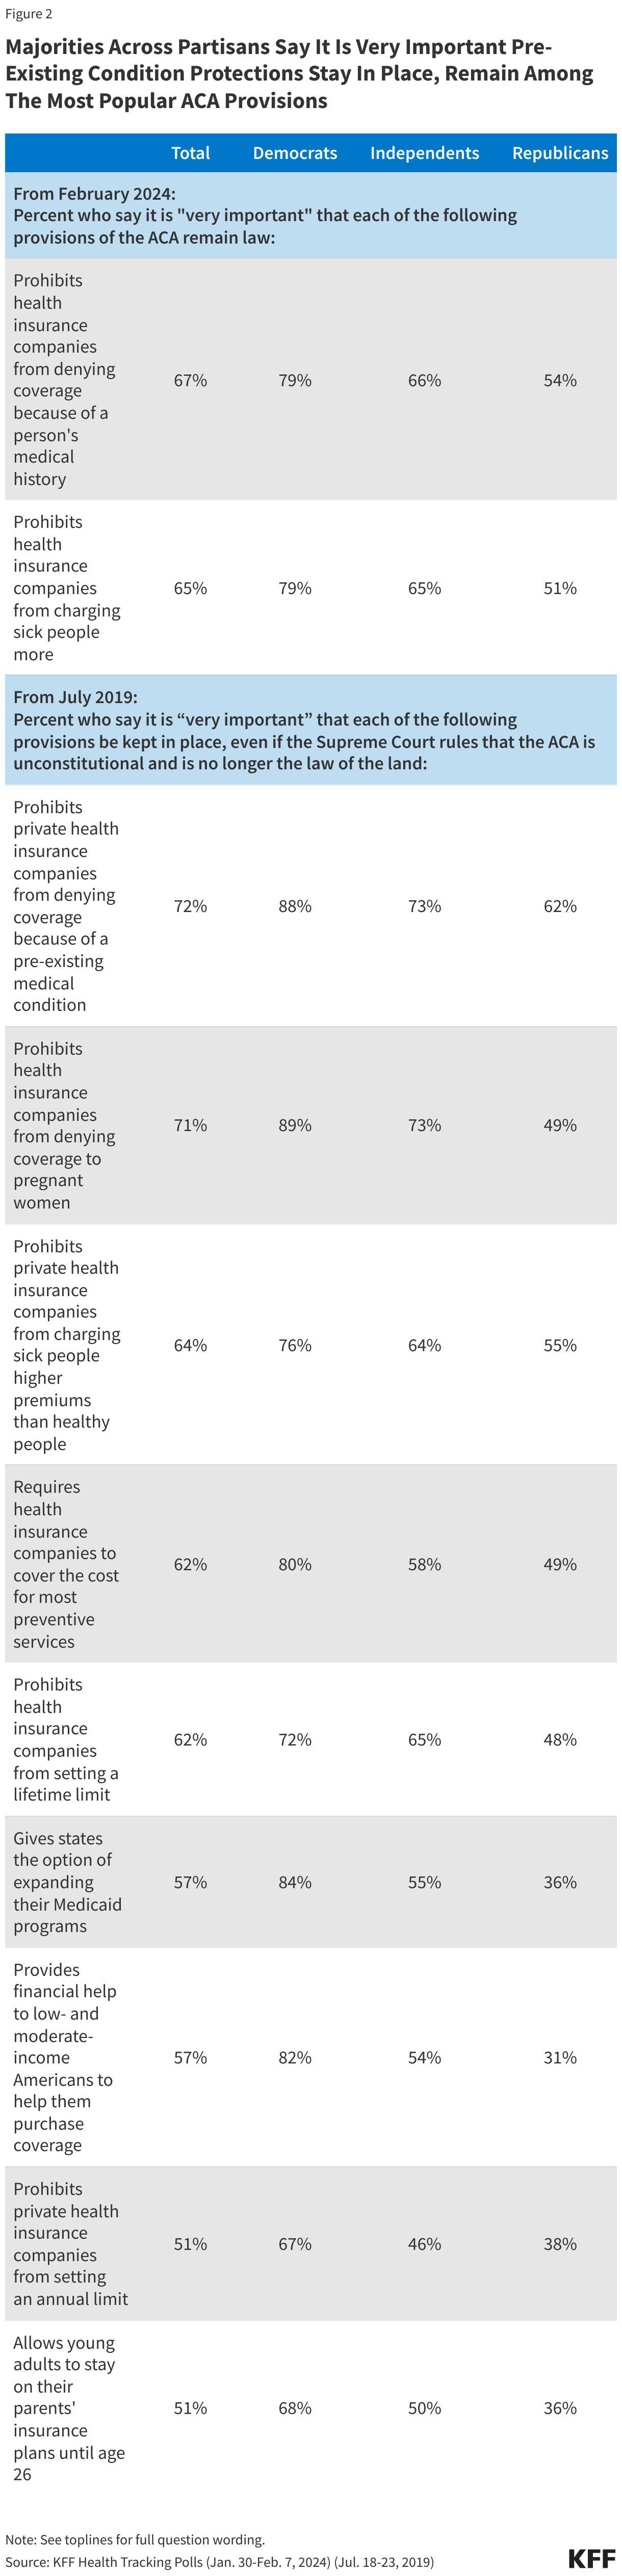
For example, the 2020 California v. Texas case challenged the legality of the individual mandate and brought special attention to the law’s protections for people with pre-existing medical conditions. These provisions prohibit insurance companies from denying coverage based on a person’s medical history (known as guaranteed issue) and prohibit insurance companies from charging those with pre-existing conditions more for coverage (known as community rating). As of February 2024, two-thirds of the public say it is “very important” for the guaranteed issue (67%) and community rating (65%) provisions to remain law, including majorities of Democrats and independents. About half of Republicans say each of these protections for people with pre-existing conditions are “very important.” Historically, majorities also say it is very important for many of the other ACA provisions to be kept in place, even if the Supreme Court ruled the ACA unconstitutional and no longer the law of the land.

Though majorities say it is very important for guaranteed issue to remain law, knowledge that this provision is part of the ACA has dropped over the past 14 years. As of February 2024, about four in ten (39%) adults are aware that the ACA prohibits insurance companies from denying coverage based on a person's medical history, compared to seven in ten adults in June 2010, shortly after the ACA’s inception.

Table showing percent of adults who say it is "very important" that specific Affordable Care Act provisions remain in place. Results shown by total adults and party identification.

#3: Pre-Existing Condition Protections Affect Large Shares of the Public

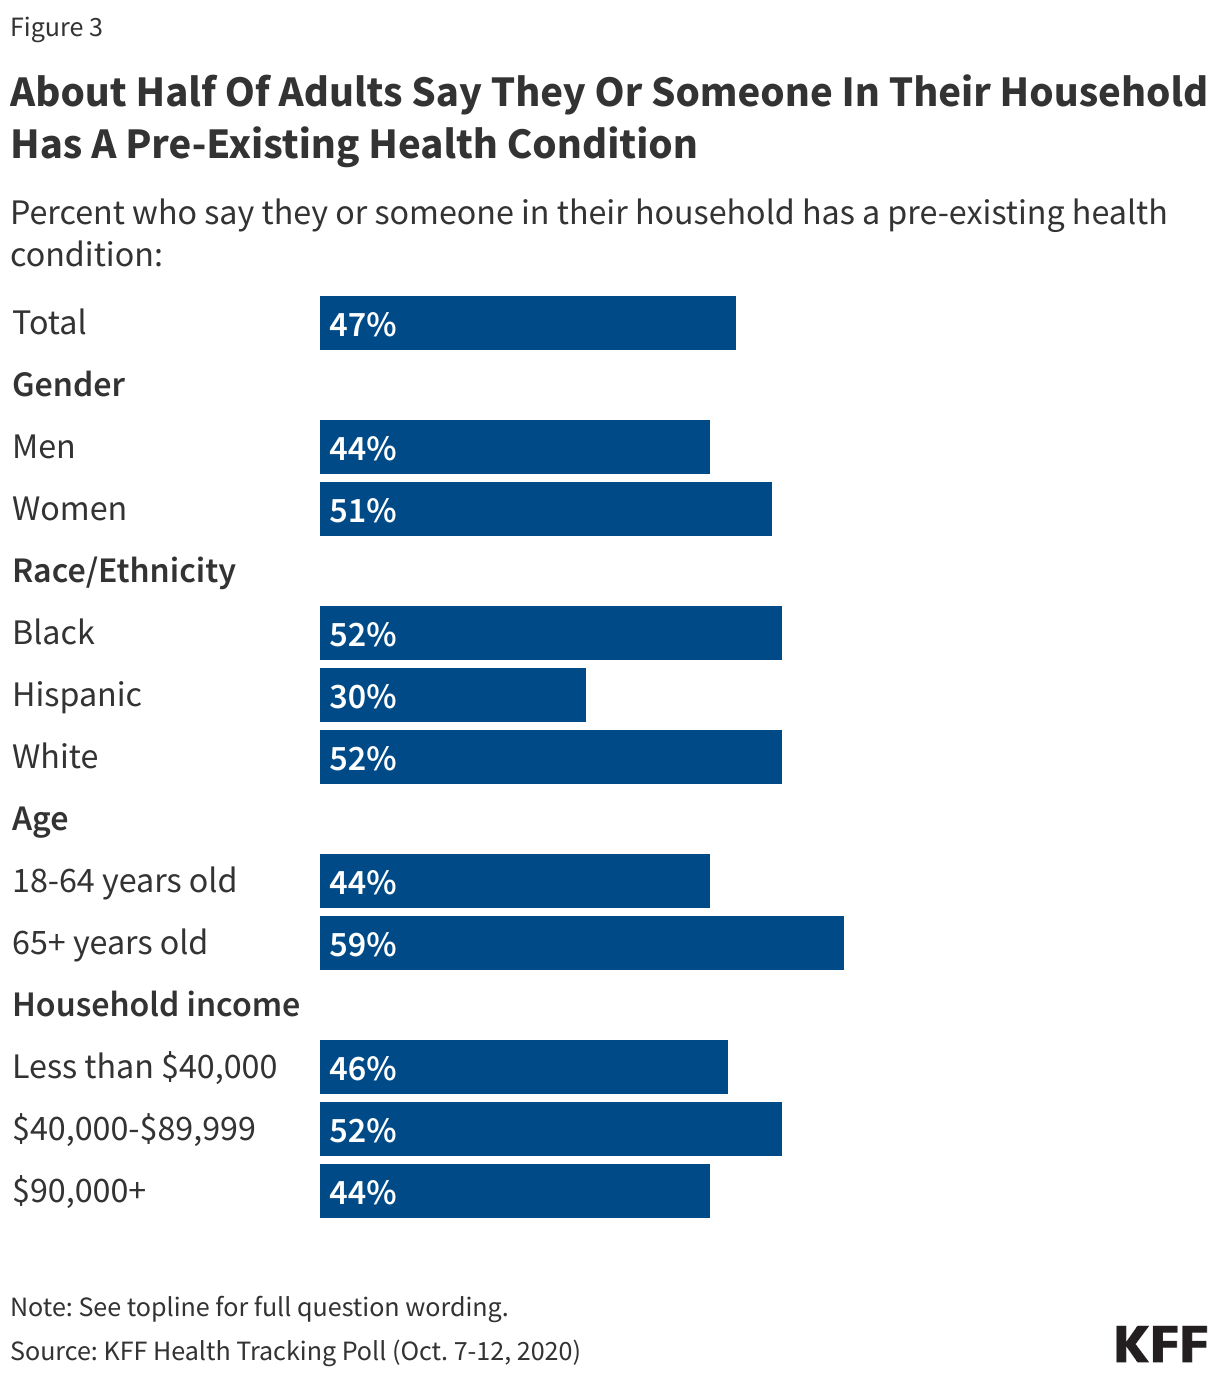
One reason why majorities across partisans may support the ACA’s protections for people with pre-existing medical conditions is that large shares of the public, regardless of age, gender, racial or ethnic identity, and income report having someone with a pre-existing condition in their household. A KFF analysis estimates that 27% of adults ages 18-64 have a pre-existing condition that would have led to a denial of insurance in the individual market prior to the implementation of the ACA. An even larger share of the public believes they or someone in their family may belong in this category. According to the KFF polling data from 2020, about half of the public say they or someone in their household suffers from a pre-existing medical condition, such as asthma, diabetes, or high blood pressure.1 

Bar chart showing percent of adults who say they or someone in their household has a pre-existing health condition. Results shown by total adults, gender, race and ethnicity, age, and household income.

#4: Those Who Say the ACA Has Helped Them Cite Increasing Access

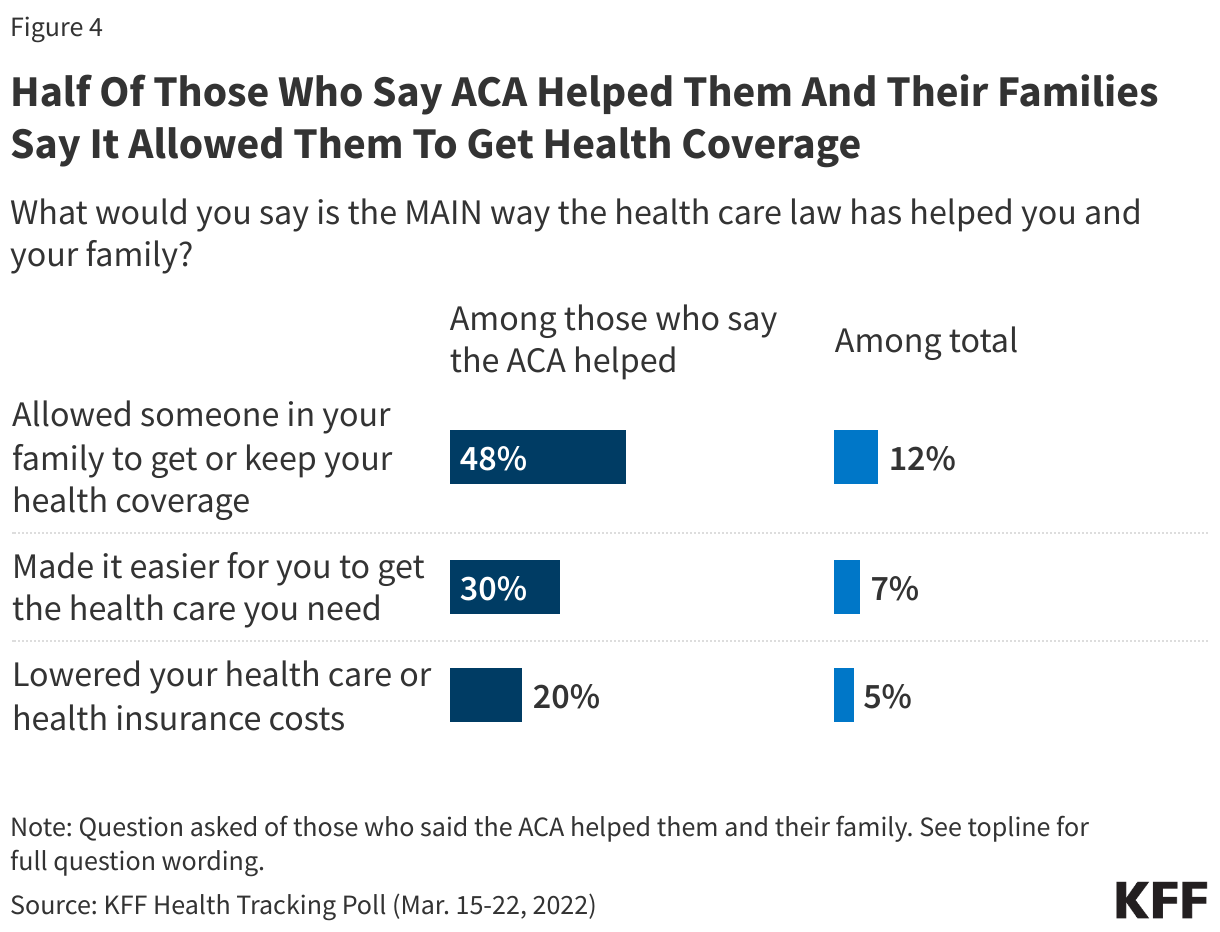
KFF polling from March 2022 shows about a quarter of the public says the ACA has helped them and their family in some way, while one in five say the law has hurt them. About half of those who say the ACA helped them say allowing someone in their family to get or keep their health coverage has been the main way the health care law has helped them (48%, or 12% of total adults). Three in ten say the law has made it easier for them to get the health care they need (7% of total) and one in five say it has lowered the cost of their health care or health insurance (5% of total).

Split bar chart showing percent of adults who say specific items were the main way the Affordable Care Act helped them and their family. Results shown among those who say the ACA helped them and among total adults.

The February 2024 Health Tracking Poll also reveals four in ten (39%) adults say the ACA has made it easier for people like them to get health insurance, while about one in four (23%) say it has made it more difficult. However this perception varies by partisanship, as Democrats are almost three times as likely as Republicans (60% v. 22%) to say the ACA has helped them in this way.

#5: Those Who Say the ACA Has Hurt Them Cite Costs

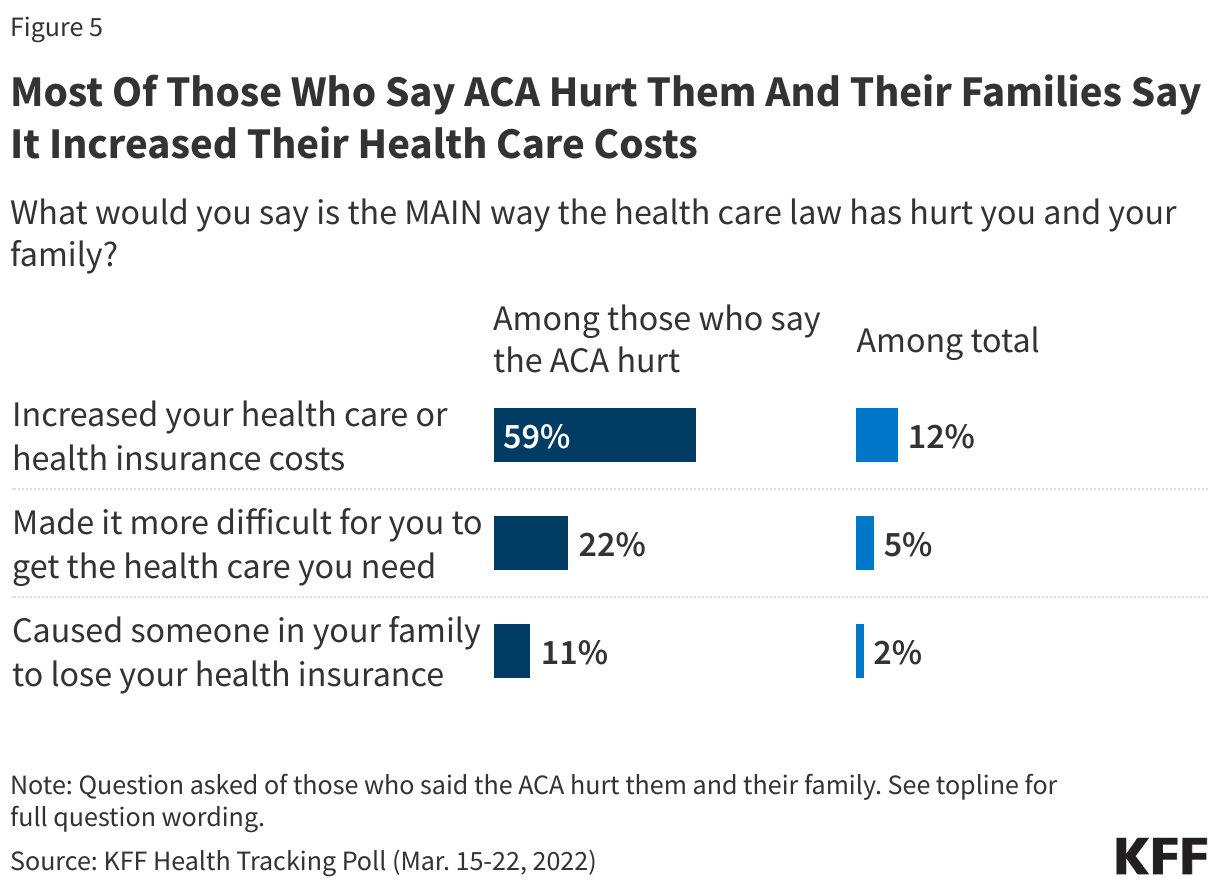
Among the one in five U.S. adults who say the ACA has hurt them and their families, most say the law has increased costs of health care or health insurance (59%, 12% of total). Smaller shares say it has made it more difficult to access care (22%, 5% of total), or caused someone in their family to lose coverage (11%, 2% of total). The high costs of health care in this country continue to be a major burden for many families.

Split bar chart showing percent of adults who say specific items were the main way the Affordable Care Act hurt them and their family. Results shown among those who say the ACA hurt them and among total adults.
  1. This estimate is a household measure of all groups and does not classify pre-existing conditions by whether they are or not a “deniable” condition. See the KFF Health Tracking Poll October 2020 topline for full question wording and details. ↩︎

Recent Trends in GLP-1 Use and Spending in Medicare

Published: Jan 30, 2026

Ahead of the Trump administration’s planned expansion of Medicare coverage for GLP-1s to treat obesity through temporary models and the availability of Medicare’s negotiated price for certain GLP-1 products beginning in 2027, new data from the Centers for Medicare & Medicaid Services (CMS) shows that use and spending for these drugs under Medicare has grown substantially in recent years, reflecting their demonstrated effectiveness at treating type 2 diabetes and other conditions. Medicare currently covers GLP-1s for type 2 diabetes, cardiovascular disease, and sleep apnea, but coverage for weight loss drugs is prohibited by law, even as GLP-1s have proved to be highly effective for this purpose (and even cost-effective, according to a recent analysis).

To address this gap in coverage for GLP-1s to treat obesity, CMS is launching a model called BALANCE (Better Approaches to Lifestyle and Nutrition for Comprehensive hEalth) under which CMS will negotiate pricing and coverage rules for GLP-1s, with the aim of expanding access to these medications and lifestyle interventions to support weight loss. The model, beginning in 2026 for Medicaid and 2027 for Medicare, is voluntary for drug manufacturers, state Medicaid programs, and Medicare Part D plans.

This analysis examines CMS’s Medicare Part D claims data from 2019 to 2024 to document the increase in the number of beneficiaries being treated with GLP-1 drugs and the growth in Medicare spending and claims for GLP-1s. Expansion of coverage under Medicare of GLP-1s to treat obesity under the BALANCE model is likely to increase utilization above current levels, as Medicare begins to meet the demand for obesity drugs among beneficiaries who have been unable to access or afford these medications to date. At the same time, the availability of Medicare’s lower negotiated price for certain GLP-1 products under the Medicare Drug Price Negotiation Program (semaglutide beginning in 2027 and dulaglutide beginning in 2028) could mitigate the increase in Medicare spending that could come about from ongoing and expanded use of these medications.

Ozempic Was Used by Two Million Medicare Part D Enrollees in 2024, Up from Fewer Than 150,000 in 2019

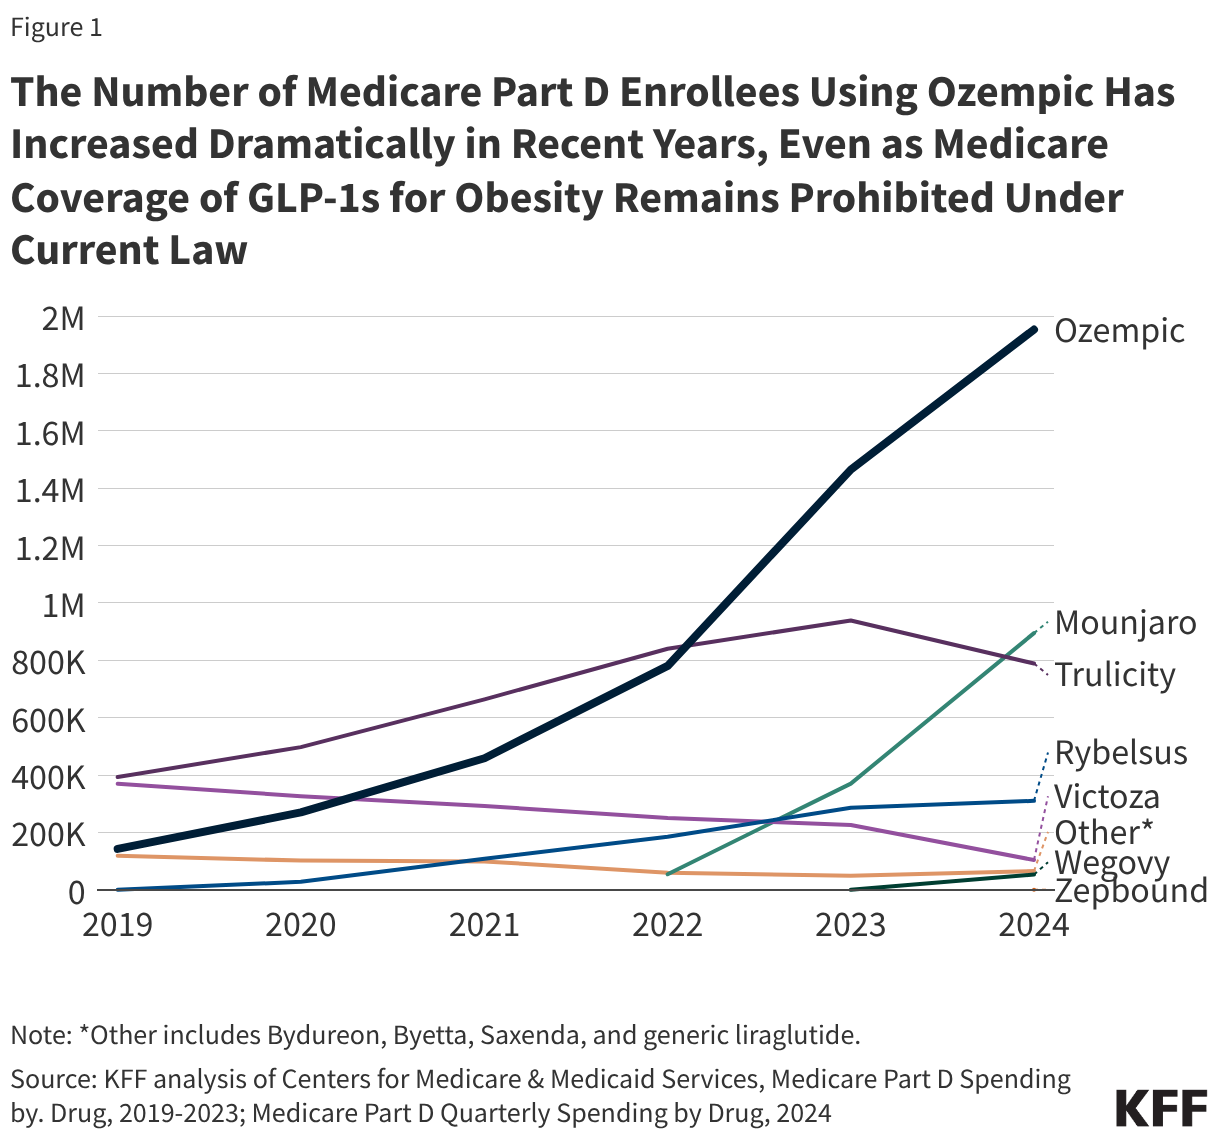
Semaglutide, the GLP-1 drug branded as Ozempic, Rybelsus, and Wegovy, was the most used GLP-1 in 2024. Two million Part D enrollees took Ozempic, which was approved by the FDA in 2017 to treat type 2 diabetes, up from fewer than 150,000 in 2019 (Figure 1). Nearly 1 million Part D enrollees took Mounjaro, approved in 2022 for type 2 diabetes, up from 54,000 in 2022. This increase reflects a pattern of growing use of newer GLP-1s, such as Ozempic and Mounjaro, while use of older products, such as Byetta (approved in 2005), Victoza (approved in 2010), and Trulicity (approved in 2014), has declined. While most GLP-1 drugs are currently available as injections, the introduction of new oral formulations, which could be easier for patients to take, could result in additional shifts in utilization among GLP-1s.

The Number of Medicare Part D Enrollees Using Ozempic Has Increased Dramatically in Recent Years, Even as Medicare Coverage of GLP-1s for Obesity Remains Prohibited Under Current Law (Line chart)

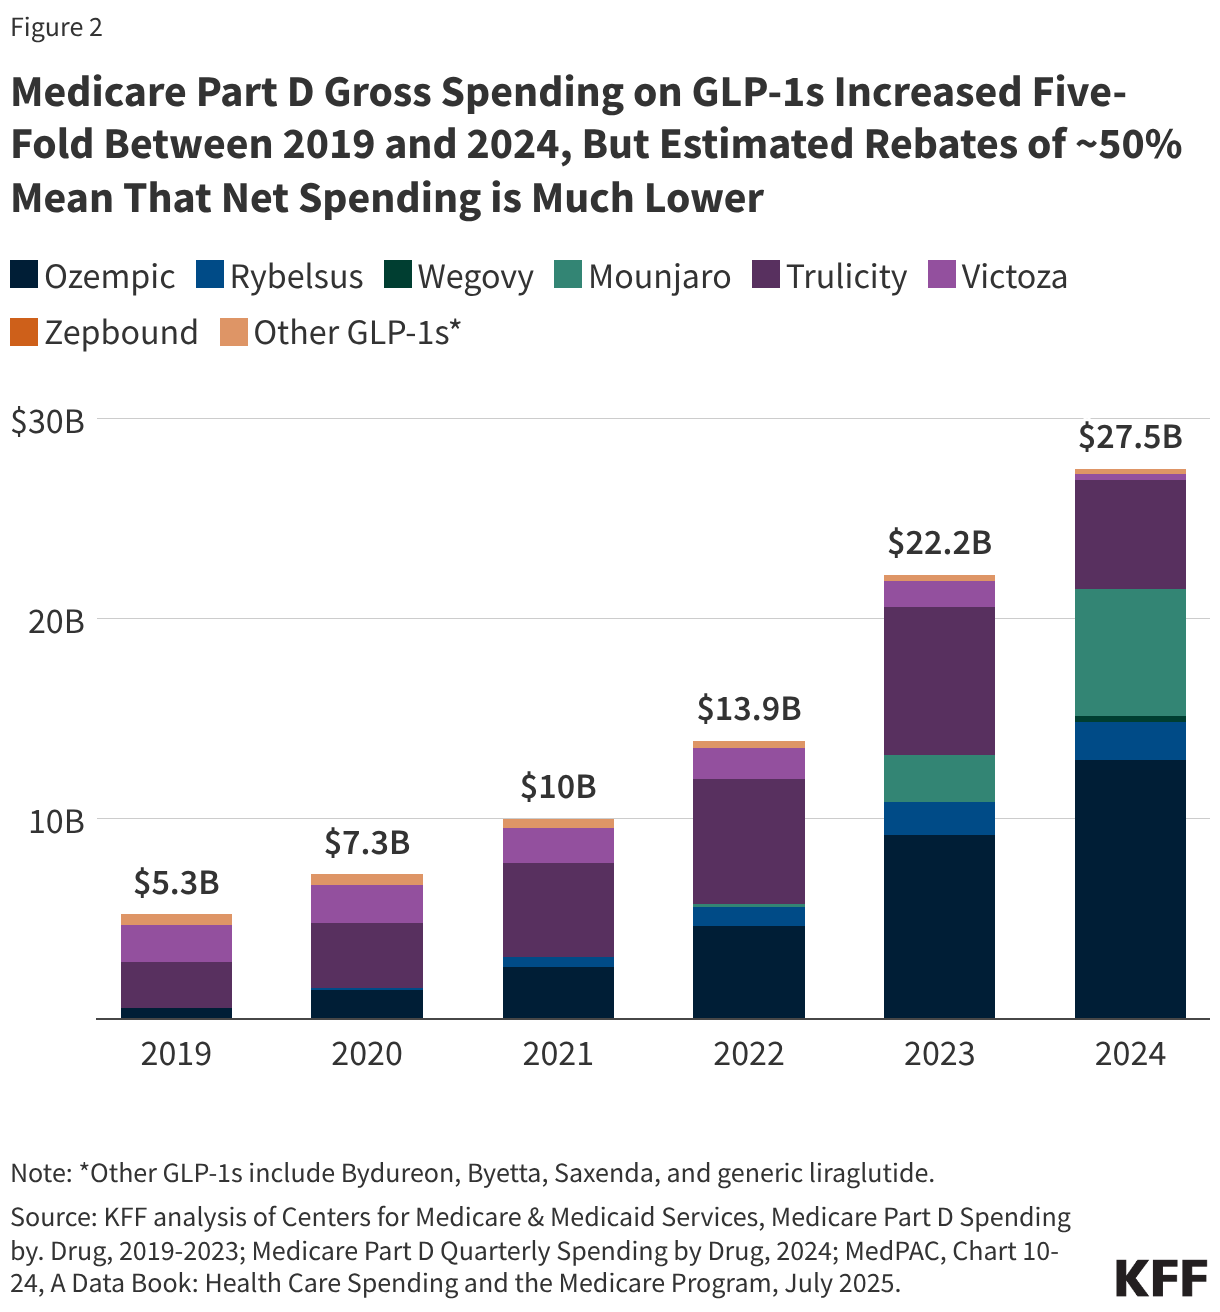
Medicare Part D Gross Spending on GLP-1s Increased Five-Fold Between 2019 and 2024, But Estimated Rebates of Around 50% Mean That Net Spending is Much Lower

Gross Medicare Part D spending on GLP-1s in 2024 (not accounting for rebates) totaled $27.5 billion, a five-fold increase from 2019, reflecting an expansion in use of GLP-1s with more recent FDA approvals for type 2 diabetes. (FDA approvals of Wegovy for cardiovascular disease and Zepbound for sleep apnea occurred in 2024 and therefore these uses are likely not reflected in Part D data through 2024.) More than half of gross spending in 2024 was on semaglutide products (Ozempic, 47%; Rybelsus, 7%; Wegovy, 1%) and nearly one fourth (23%) was for Mounjaro. Gross spending overstates the true cost of these products to the Medicare program, however. According to estimates from MedPAC, negotiated rebates for diabetic therapy were equal to or greater than 50% in 2023. Assuming rebates of 50% across all GLP-1 products in 2024 would mean net spending of around $14 billion in 2024.

Medicare Part D Gross Spending on GLP-1s Increased Five-Fold Between 2019 and 2024, But Estimated Rebates of ~50% Mean That Net Spending is Much Lower (Stacked column chart)

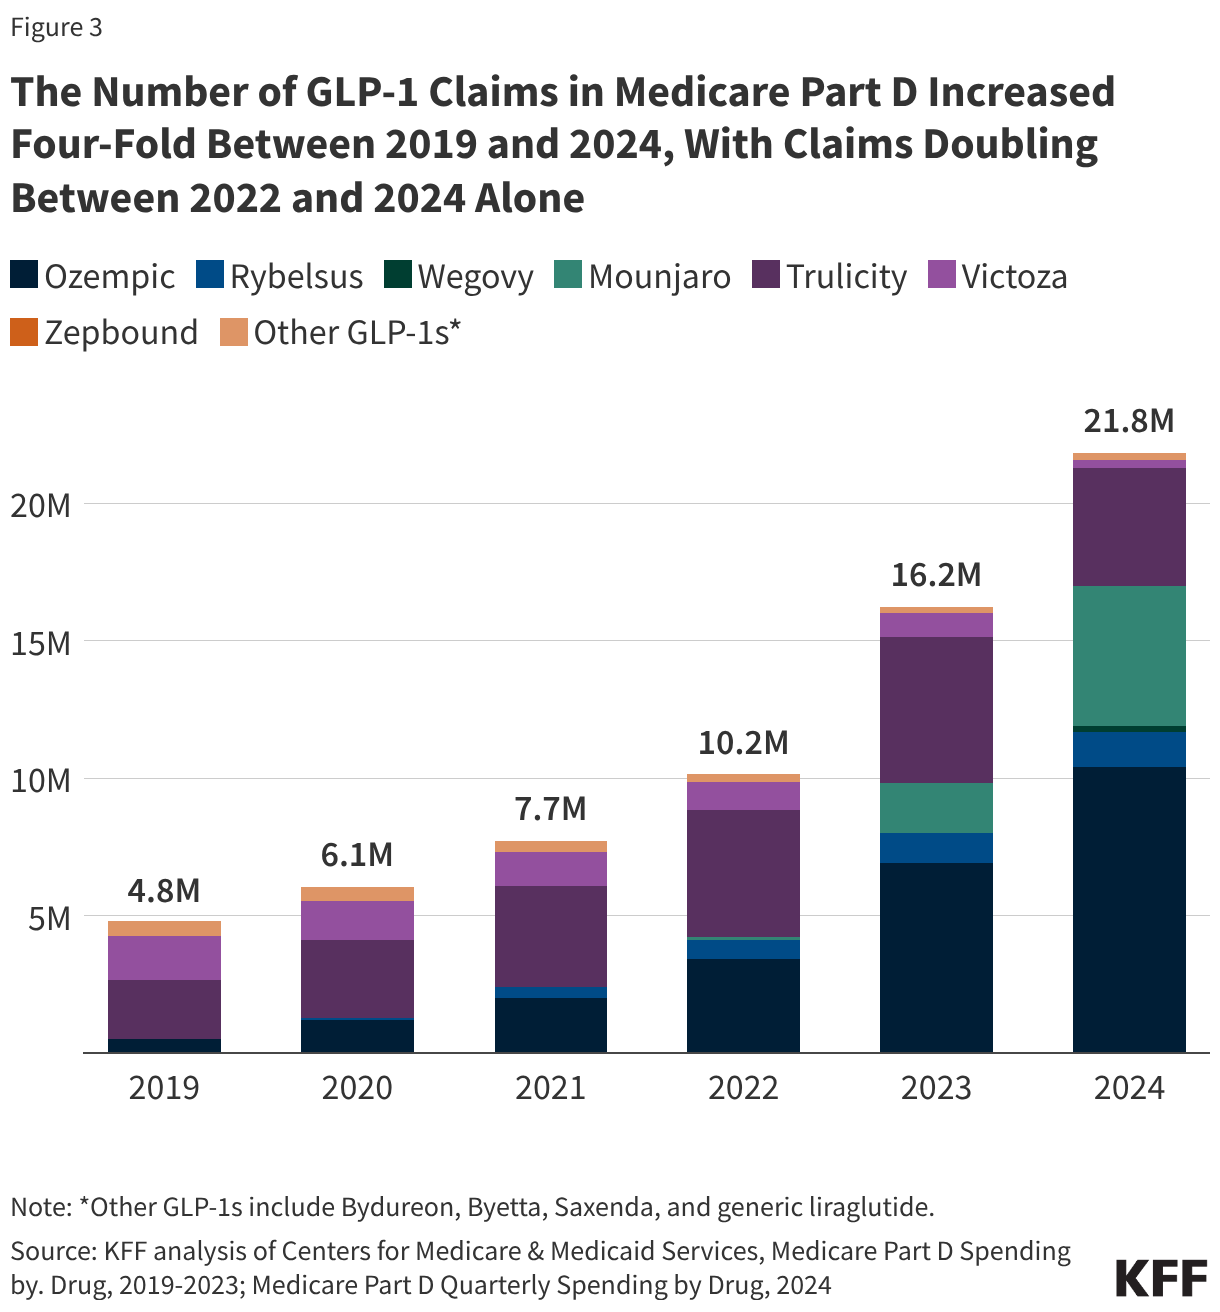
Claims for GLP-1s Increased Four-Fold Between 2019 and 2024

In accordance with an increase in both the number of Medicare Part D enrollees using GLP-1s and spending on these products, the number of claims for GLP-1s increased four-fold between 2019 and 2024, from 4.8 million to 21.8 million, with claims doubling between 2022 and 2024 alone. More than 10 million claims for Ozempic were submitted in 2024, up from 524,000 in 2019 (an 82% average annual growth rate) and another 5.1 million for Mounjaro, up from 122,000 in 2022 (average annual growth of 549%).

The Number of GLP-1 Claims in Medicare Part D Increased Four-Fold Between 2019 and 2024, With Claims Doubling Between 2022 and 2024 Alone (Stacked column chart)

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

A Closer Look at Nebraska, the First State Planning to Implement a Medicaid Work Requirement

Authors: Amaya Diana and Anna Mudumala
Published: Jan 30, 2026

In December, Nebraska was the first state to announce that it would be enforcing Medicaid work requirements early, starting May 1, 2026. The 2025 reconciliation law requires states to condition Medicaid eligibility for adults in the ACA Medicaid expansion group and enrollees in partial expansion waiver programs (Georgia and Wisconsin) on meeting work requirements starting January 1, 2027; however, states have the option to implement requirements sooner through a state plan amendment (as is the case for Nebraska) or through an approved 1115 waiver. Implementing work requirements will require complex changes to eligibility and enrollment systems, as well as enrollee outreach and education, staff training, and coordination with managed care plans, providers, and other stakeholders. Early reports from the state during its recent January Medicaid Advisory Committee (MAC) meeting and data from KFF’s Medicaid work requirements tracker provide initial insight into how Nebraska is preparing to implement Medicaid work requirements. Similar information from MAC meetings in other states and data on the KFF tracker can be helpful to assess how other states may implement new requirements as well. 

Most Medicaid adults in Nebraska under age 65 who will be subject to the new work requirements are working already or attending school. As of March 2025, there were about 72,000 expansion enrollees in Nebraska who could be affected by the new requirements. KFF analysis indicates that roughly 65% of Medicaid adults without dependent children in Nebraska who could be subject to work requirements work 80 or more hours per month or are attending school. In addition, many enrollees who are not working the required hours will likely qualify for exemptions from the new work requirements.

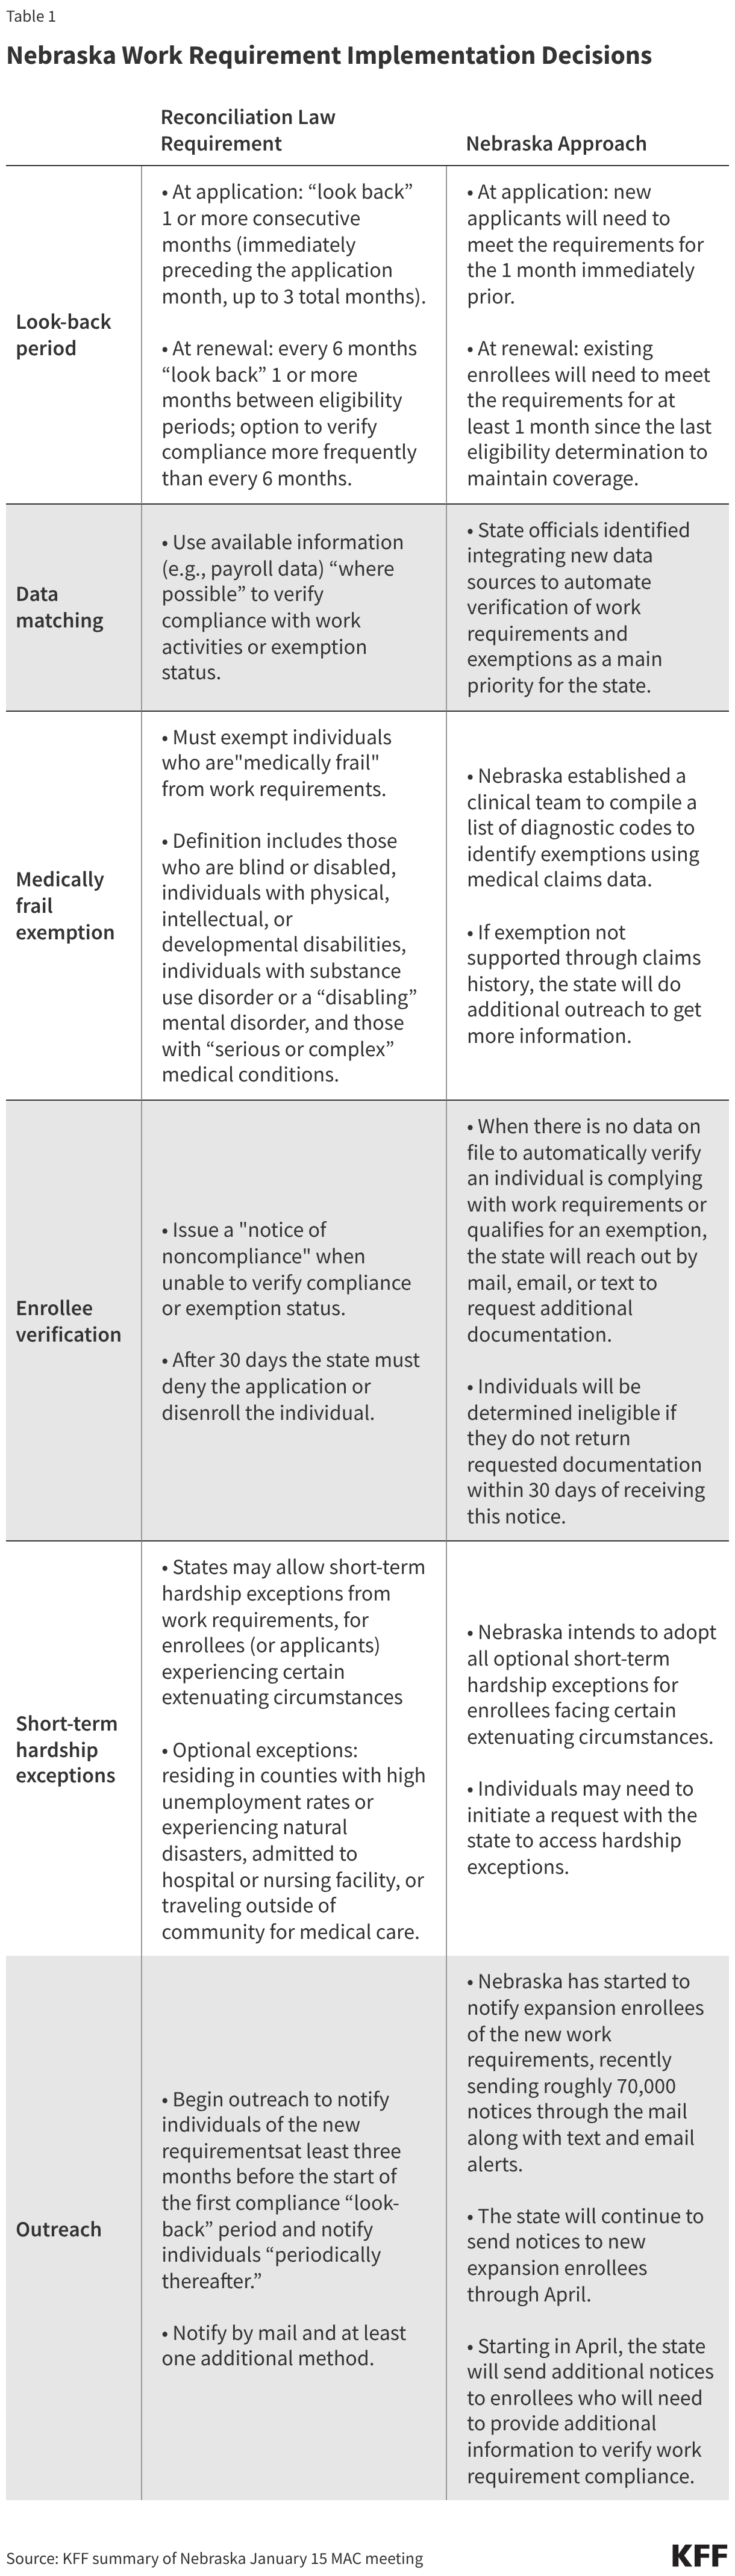
In a recent Medicaid Advisory Committee (MAC) meeting, Nebraska provided a first look into how the state is planning to implement work requirements. All states are required to have a Medicaid Advisory Committee to advise the State Medicaid agency about health and medical care services. These groups include Medicaid enrollees, advocates, and providers. In its January 15, 2026 meeting, Nebraska state officials provided early insight into key decisions related to work requirements and look-back periods, data matching, medically frail exemptions, enrollee verification, short-term hardship exceptions, and outreach (Table 1). State officials also confirmed that the state does not intend to hire or increase staffing levels to facilitate implementation of work requirements or other eligibility changes.

Nebraska Work Requirement Implementation Decisions (Table)

There remain multiple operational and implementation issues the state will need to resolve in the next four months. State officials emphasized that conversations with the federal government are ongoing, and that Centers for Medicare and Medicaid Services (CMS) staff had recently travelled to Nebraska to plan implementation with state officials. As part of the MAC meeting discussion, state officials noted areas where there is ongoing work to identify data sources to verify compliance or exemption status:

  • Volunteer activities. Officials acknowledged they had not yet determined how volunteer activities will be defined or how volunteer activities could be identified through data matching. Current guidance from CMS does not clearly outline what types of volunteer activities count towards compliance with Medicaid work requirements.
  • Education activities. Officials said the state is working on specifics for defining hours of educational activity using course credit hours. The state is also exploring data matching for educational activities, including higher education enrollment data.
  • Work verification. Data matching for work hours was not discussed during the meeting, though officials confirmed that, as required by the reconciliation law, individuals can meet the work requirement if they are working and earn the equivalent of the federal minimum wage multiplied by 80 hours in a qualifying month.
  • Number of enrollees affected. State officials could not yet provide internal estimates of how many enrollees could already be identified as in compliance with the new requirements using currently available data sources, but explained they are currently running models to see who they can identify as being in compliance or exempt from Medicaid work requirements.

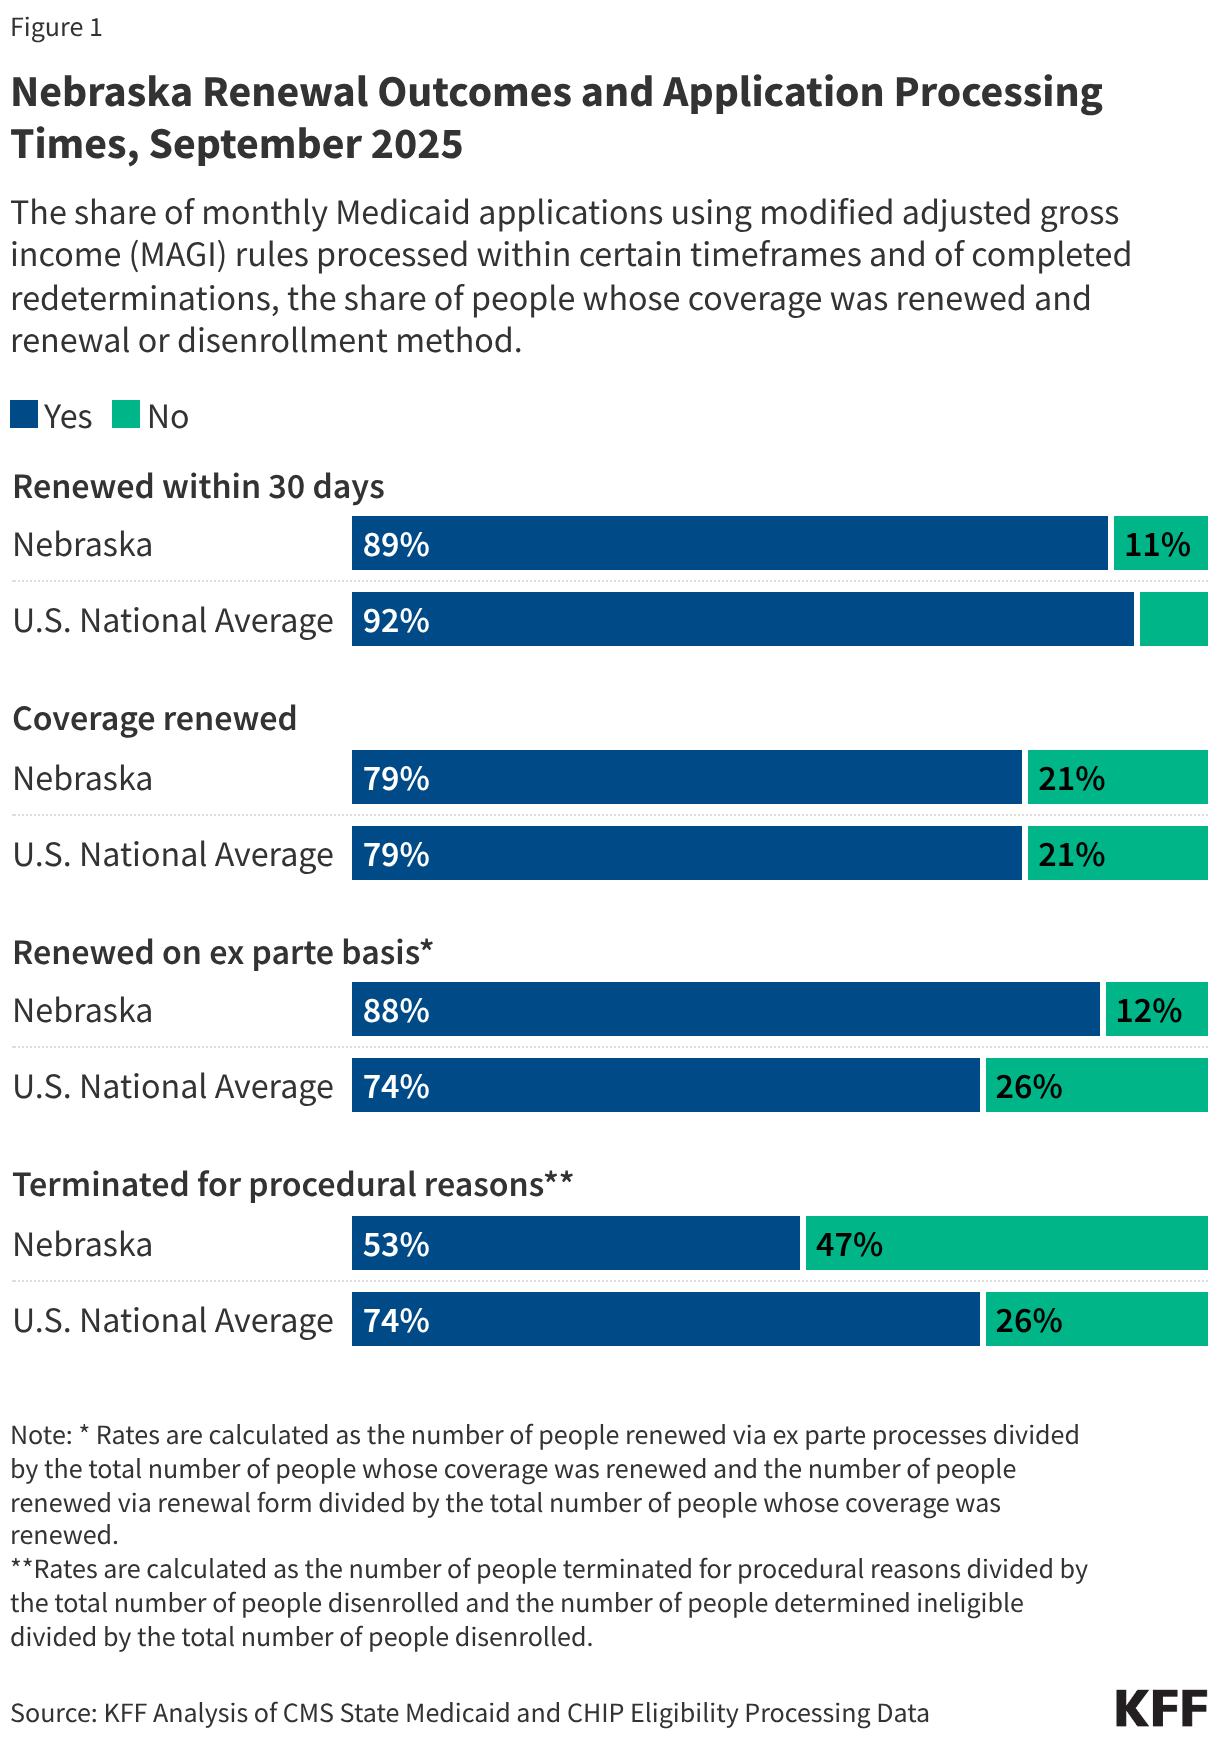
KFF is tracking metrics related to Medicaid enrollment, renewal outcomes, and application processing times that can provide insight into a state’s potential readiness to implement data matching and other necessary system changes. As of September 2025, Nebraska was performing in line or better across several renewal metrics compared to the United States national average (Figure 1). Nearly nine in ten applications were processed within 30 days and eight in ten individuals going through a Medicaid eligibility redetermination had their coverage renewed. Of people who retained coverage, 88% were renewed via ex parte processes (meaning the state verifies ongoing eligibility through available data sources before sending a renewal form or requesting documentation from an enrollee), although this percentage in September 2025 was higher than the average of 69% across the prior 6 months. Among those who were disenrolled, 53% were terminated for procedural reasons (meaning an individual was disenrolled because they did not complete the renewal process). While these metrics provide insight into Nebraska’s Medicaid eligibility systems, they are not the only indicators or predictors of successful implementation of work requirements, which will also require enrollee outreach and education, staff training, and coordination with managed care plans, providers, and other stakeholders.

Nebraska Renewal Outcomes and Application Processing Times, September 2025 (Stacked Bars)

As states implement work requirements, ongoing monitoring can help assess how processes are working and identify areas of concern. Central to that oversight is timely data on renewal outcomes, including data on disenrollments related to work requirements. While available data (highlighted above) from CMS can be helpful, these data are not timely enough for real-time monitoring and they do not isolate outcomes for the expansion population. States can fill that gap by reporting more timely data on application and renewal outcomes that include breakouts for individuals subject to work requirements. During the MAC meeting, state officials in Nebraska communicated their intention to be transparent in reporting how many enrollees are disenrolled.

Potential Impact of the Federal Pause on Immigrant Visas From 75 Countries on the U.S. Health Care Workforce

Published: Jan 29, 2026

As part of broader efforts to reduce immigration, the U.S. Department of State (DOS) recently announced that it will pause issuance of all immigrant visas for individuals from 75 countries. This analysis shows that workers from 69 of the 75 countries affected by the pause for which data are available make up nearly one in ten (8%) of the U.S. health care workforce. The pause will likely reduce the supply of workers and particularly health care workers in the U.S., which could exacerbate existing health care worker shortages. Shortages are likely to be compounded by other policies limiting immigration into the U.S. as well as ongoing deportation efforts. Estimates suggest the Trump administration’s policies could reduce legal immigration to the U.S. by 33% to 50% over four years.

On January 14, 2026, the DOS announced that it will pause processing of immigrant visas for individuals from 75 countries who it identified as at, “high risk for use of public benefits” and becoming a public charge. (See Methods for full list of impacted countries). This policy is part of broader efforts to expand public charge policies.The DOS indicates that the pause is being implemented to ensure “immigrants must be financially self-sufficient and not be a financial burden to Americans”. However, the DOS has not provided details about the process used to identify countries subject to the pause. Moreover, few immigrants are eligible for federal benefits due to longstanding restrictions. For example, most lawfully present immigrants have to wait five years after obtaining a “qualified” immigration status to be eligible for federal programs including Medicaid and the Supplemental Nutrition Assistance Program (SNAP).  

The pause went into effect on January 21, 2026, for nationals from the 75 countries applying for immigrant visas. Immigrant visas allow an individual to live and work in the U.S. on a permanent basis and can provide a pathway to citizenship. Examples of immigrant visas include family-based visas (when a U.S. citizen or lawful permanent resident (LPR or “green card” holder) sponsors a family member for permanent residency), certain types of employment-based  visas, as well as refugee visas (although entry of refugees to the U.S. has already largely been eliminated through executive action). Individuals applying for non-immigrant visas such as a student visa, tourist visa, or temporary work visa like H-1B are not impacted by the pause. The DOS states that, during this pause, applicants from impacted countries may submit visa applications and attend visa interviews, but that it will not issue any immigrant visas. The pause does not impact immigrants from the 75 countries who are already present in the U.S.

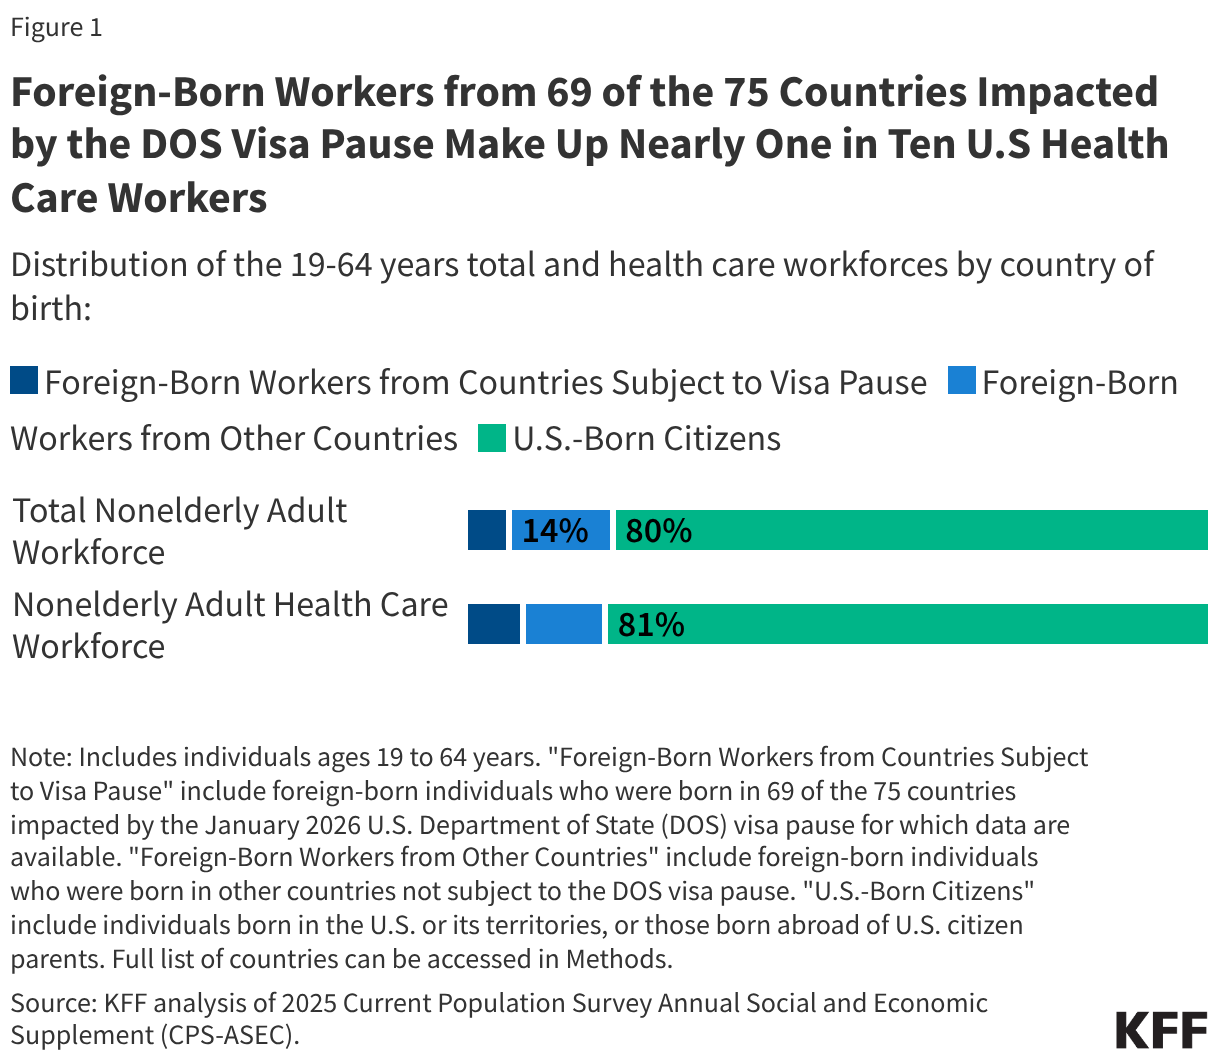
Foreign-born workers from 69 of the 75 countries impacted by the DOS visa pause for which data are available make up nearly one in ten (8%) of health care workers in the U.S. Based on KFF analysis of 2025 Current Population Survey data, there were 7.8 million foreign-born workers (ages 19 to 64) from 69 of the 75 countries impacted by the visa pause as of 2025, including 1.2 million health care workers. A little over half (55%) of health care workers from these countries are employed in health care support occupations such as home health aides and nursing aides, and the remaining 45% are in health care practitioner and technical occupations such as physicians, surgeons, and nurses. These workers include individuals who may have arrived on immigrant or non-immigrant visas since the data do not include information on visa type. Separate data for the remaining six countries affected by the pause (The Gambia, Kosovo, Kyrgyz Republic, Rwanda, South Sudan, and Tunisia) were not available. Among foreign-born workers from the 69 countries, those from Haiti (13%), Jamaica (10%), and Nigeria (9%) made up about one in three (32%), or the highest shares, of health care workers. Workers from 69 of the 75 countries affected by the DOS visa pause accounted for 6% of the total U.S. adult workforce and 8% of health care workers under age 65 (Figure 1). Immigrants from other countries not impacted by the pause accounted for 14% of the U.S. adult workforce and 11% of health care workers, and U.S.-born citizens accounted for the remaining eight in ten workers.

Foreign-Born Workers from 69 of the 75 Countries Impacted by the DOS Visa Pause Make Up Nearly One in Ten U.S Health Care Workers (Stacked Bars)

Methods

Data source: These findings are based on KFF analysis of the 2025 Current Population Survey Annual Social and Economic Supplement (CPS-ASEC). The CPS is a nationally representative U.S. household survey sponsored jointly by the U.S. Census Bureau and the U.S. Bureau of Labor Statistics and is the “primary source of labor force statistics for the population of the United States”.

Identifying foreign-born workers from impacted countries in CPS-ASEC: Foreign-born workers are identified as those between ages 19 and 64 who report their citizenship group as either “foreign born, US cit by naturalization” or “foreign born, not a US citizen”. Those who further indicate their country of birth as being one of the 75 countries impacted by the DOS visa pause (listed below) are included in the sample of foreign-born workers from countries subject to the visa pause. Of note, CPS does not include country of birth data separately for 6 of the 75 countries impacted by the DOS visa pause, namely The Gambia, Kosovo, Kyrgyz Republic (Kyrgyztan), Rwanda, South Sudan, and Tunisia.

List of impacted countries: Afghanistan, Albania, Algeria, Antigua and Barbuda, Armenia, Azerbaijan, Bahamas, Bangladesh, Barbados, Belarus, Belize, Bhutan, Bosnia and Herzegovina, Brazil, Burma, Cambodia, Cameroon, Cape Verde, Colombia, Cote d’Ivoire, Cuba, Democratic Republic of the Congo, Dominica, Egypt, Eritrea, Ethiopia, Fiji, The Gambia, Georgia, Ghana, Grenada, Guatemala, Guinea, Haiti, Iran, Iraq, Jamaica, Jordan, Kazakhstan, Kosovo, Kuwait, Kyrgyz Republic, Laos, Lebanon, Liberia, Libya, Moldova, Mongolia, Montenegro, Morocco, Nepal, Nicaragua, Nigeria, North Macedonia, Pakistan, Republic of the Congo, Russia, Rwanda, Saint Kitts and Nevis, Saint Lucia, Saint Vincent and the Grenadines, Senegal, Sierra Leone, Somalia, South Sudan, Sudan, Syria, Tanzania, Thailand, Togo, Tunisia, Uganda, Uruguay, Uzbekistan, and Yemen(Source: DOS).

Identifying health care workers in CPS-ASEC: Health care workers are identified as those whose detailed occupation in CPS-ASEC is reported as either “healthcare practitioner and technical occupations” or “healthcare support occupations”.

VOLUME 39

Abortion Pill Safety Decisions by FDA Were Science-Based, New JAMA Study Finds


Highlights

A new study found that Food and Drug Administration (FDA) decisions about the abortion pill mifepristone consistently followed scientific evidence, even as misleading claims about the drug’s safety continue to shape public understanding.

And Google removed some health AI summaries after a Guardian investigation reported that AI-generated summaries for search results about multiple health topics, including cancer screening, liver disease, and mental health conditions, shared false and potentially dangerous health information. While the full extent of inaccurate health information in these AI-generated summaries is unclear, patient advocacy organizations described the examples as “dangerous” and “alarming.”


What We’re Watching

Claims That the FDA Failed to Properly Evaluate Mifepristone Persist as New Study Finds Decisions Were Science-Based 

As FDA leadership initiates a new safety review of mifepristone following claims by abortion opponents that the drug was not adequately evaluated before it was granted approval, a new study published in JAMA examining more than 5,000 pages of internal FDA documents from 2011 to 2023 finds that agency decisions were consistently driven by scientific evidence, not politics. The study found that agency leaders almost always followed the recommendations of career scientists, repeatedly reviewed safety data, and reaffirmed that mifepristone is safe while making cautious changes to access. Despite this detailed analysis documenting the rigor of the FDA’s review process, the Senate’s Health, Education, Labor, and Pensions (HELP) Committee held a hearing this month framed as an inquiry into the abortion pill’s safety, with statements describing mifepristone as putting women in “serious danger.” Evidence continues to demonstrate that mifepristone is a safe medication. KFF polling shows that while twice as many adults say mifepristone is “safe” (42%) than say it is “unsafe” (18%) when taken as directed by a doctor, four in ten express uncertainty over the pill’s safety. Perception of the abortion pill’s safety has declined since 2023 among the public overall (42% view as safe now v. 55% in 2023) and among women ages 18 to 49 (41% view as safe now v. 59% in 2023).

Polling Insights:

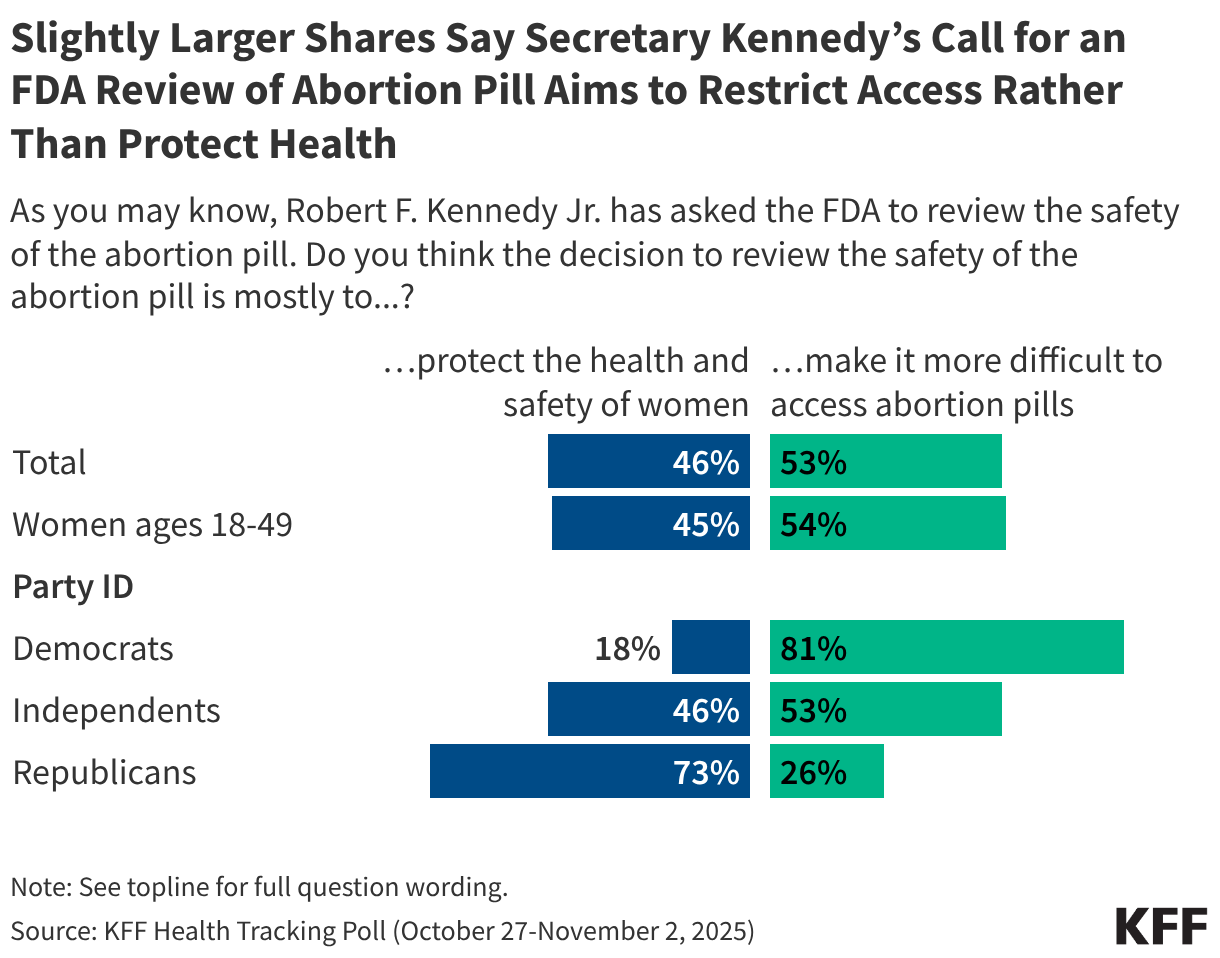
KFF’s November 2025 Health Tracking Poll found that the public is largely divided over the intention underlying the FDA’s review of mifepristone. Just over half (53%) of adults and a similar share of women of reproductive age say that Secretary Kennedy’s decision to have the FDA review the safety of the abortion pill is mostly to “make it more difficult to access abortion pills,” while a somewhat smaller share of the public say the decision is mostly to “protect the health and safety of women” (46%).

Views on FDA’s review of mifepristone are largely shaped by partisanship, with most Democrats (81%) saying the decision is largely about curbing access to abortion pills and most Republicans (73%) saying the decision is mostly about protecting the health of women.

Split bar chart showing share of adults who believe RFK Jr.'s call for an FDA review of mifepristone is to protect the health and safety of women versus make it more difficult to access abortion pills. Results shown by total, women of reproductive age, and party.

U.S. Withdraws from International Health Organizations as Trust in Public Health Institutions Declines

The U.S. withdrawal from the World Health Organization took effect this month, with WHO Director-General Tedros Adhanom Ghebreyesus warning that the decision "makes the U.S. unsafe" and "makes the rest of the world unsafe" by cutting access to disease surveillance and emergency response systems. The withdrawal is part of broader U.S. disengagement from international health efforts, including the recent announcement that the U.S. is withdrawing from 31 U.N. entities such as the U.N. Population Fund, the lead U.N. agency focused on global population and reproductive health. Public opinion data suggests the decision lands amid declining and polarized public confidence in the WHO itself. According to an April 2024 poll from Pew Research, about six in ten U.S. adults believed the U.S. benefitted from its membership in the WHO, fewer than the share who said the same in 2021, including an 8 percentage point decrease in the share who say the U.S. benefitted a "great deal." These concerns reflect institutional and diplomatic trust and intersect with broader trust challenges in health. The withdrawal occurs as the U.S. public’s trust in federal health agencies has continued to erode.  As global health partnerships change, health communicators may benefit from tracking changes in trust in health agencies to better understand where audiences turn to for health information.

Fraudulent Ads on Social Media Continue Despite Enforcement Measures 

Fraudulent advertising on social media continues to expose users to misleading and dangerous health claims, impacting how people assess and trust health information online. In early January, the Better Business Bureau (BBB) issued a “scam alert” about fraudulent ads using AI-generated videos of celebrities to promote fake weight-loss products, including unauthorized endorsements for supplements claiming to be GLP-1 medications. The BBB reported receiving more than 170 reports about one such product, with customers spending hundreds of dollars after seeing the fraudulent ads. The use of celebrity likenesses and medical terminology may increase the perceived credibility of these claims, even when the products are not legitimate treatments. The persistence of these false health advertisements is part of broader challenges platforms face in content moderation, with recent investigations finding thousands of deceptive ads remaining active despite prior enforcement. A Reuters investigation also reported that Meta allowed a high number of ads from Chinese partners, including ads for fake health supplements, prioritizing revenue while some enforcement measures were delayed or paused. As misleading health advertising continues, KFF will continue monitoring the types of health information that the public reports seeing and trusting on social media to better inform health communicators of when to intervene.


AI & Emerging Tech

Google’s AI Overviews in Search Results May Give Harmful Health Information

What's happening?

An investigation conducted by The Guardian found that the artificial intelligence (AI)-generated summaries that appear at the top of Google search results, called “AI Overviews,” at times provided inaccurate and misleading information about health topics, potentially giving users false reassurance about serious illness. The Guardian found that the overviews wrongly advised people with pancreatic cancer to avoid high-fat foods, provided misleading information about liver blood test results, and incorrectly identified pap smears as screenings for vaginal cancer. Since the investigation was published, Google removed some AI health summaries tied to specific search queries, but similar prompts can still trigger AI-generated results and broader risks from AI-produced health information remain.

How often do people encounter and trust these overviews?

  • July 2025 polling from the Annenberg Public Policy Center found that nearly two-thirds of Americans who search for health information online had seen AI-generated responses at the top of search results, and most who see these responses consider them at least somewhat reliable, though just 8% consider them “very reliable.” Among adults who have seen AI-generated responses when searching for health information online, about three in ten said the AI responses provided them the answer they needed either “always” or “often.” At the same time, most adults who see these AI-generated responses to health inquiries said they either always or often continue searching by following links to specific websites or other resources.
  • A qualitative study published in the Journal of Medical Internet Research found that participants often skipped these overviews in favor of traditional search results, with some expressing skepticism about them because of a lack of sourcing. Even participants who read the AI-generated summaries continued scrolling to review other results rather than stopping their search, suggesting that some users are adopting a “trust but verify” approach to AI for health information.

Why this matters

The continued prevalence of AI-generated health information, which can contain misleading and harmful advice, suggests a need for both better safeguards from technology companies and clear guidance from health communicators about how to critically evaluate AI-generated health information. Even as research indicates that some users may skip these overviews or try to independently verify their contents, communicators should be aware that patients may be using these AI overviews as starting points for health research.

About The Health Information and Trust Initiative: the Health Information and Trust Initiative is a KFF program aimed at tracking health misinformation in the U.S., analyzing its impact on the American people, and mobilizing media to address the problem. Our goal is to be of service to everyone working on health misinformation, strengthen efforts to counter misinformation, and build trust. 


View all KFF Monitors

The Monitor is a report from KFF’s Health Information and Trust initiative that focuses on recent developments in health information. It’s free and published twice a month.

Sign up to receive KFF Monitor
email updates


Support for the Health Information and Trust initiative is provided by the Robert Wood Johnson Foundation (RWJF). The views expressed do not necessarily reflect the views of RWJF and KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities. The data shared in the Monitor is sourced through media monitoring research conducted by KFF.