The Legal and Policy Landscape of Crisis Pregnancy Centers 

Published: Sep 30, 2026

Key Takeaways

  • There are an estimated 2,400 to 2,800 Crisis Pregnancy Centers (CPCs) in the US. These sites, also referred to as Pregnancy Centers, are established to dissuade pregnant people from seeking abortion care and are often associated with or established by faith-based or anti-abortion organizations. They usually attract clients by offering free pregnancy tests, ultrasounds, and material goods like diapers or clothing.  
  • CPCs largely lack oversight of how they handle client data, and clients have limited remedies if their data is leaked. While CPCs typically advertise or position themselves as medical clinics, the vast majority are not medical facilities. CPCs usually collect confidential health information from clients like pregnancy status or sexual history, but they are not subject to the federal medical privacy law known as the Health Insurance Portability and Accountability Act (HIPAA) because they do not bill insurance for their services or electronically transmit claims.  
  • Attempts to regulate CPCs have largely been unsuccessful in the courts. Citing CPC’s First Amendment protections, multiple courts, including the U.S. Supreme Court, have sided with CPCs against attorney general investigations, state laws designed to regulate CPCs, and private-sector actions to inform the public about their anti-abortion mission.  
  • In response to these legal challenges and with support from the Alliance Defending Freedom, a conservative Christian legal advocacy organization, some states have enacted legislation prohibiting state governments from interfering with the expression and association rights of CPCs or restricting CPCs’ ability to provide certain services.  
  • On the federal side, the Trump administration and anti-abortion legislators have prioritized CPC expansion. On Mother’s Day 2026, HHS established a new website, moms.gov, and it spotlights CPCs as a resource for pregnant people without identifying their anti-abortion mission and limited provision of services. The administration also opened the door to the possibility of extending federal funding support to CPCs through the federal Title X family planning program, through the program’s most recent funding guidelines, even though CPCs do not provide contraceptive services or supplies. 

Introduction

On Mother’s Day 2026, the Trump administration launched moms.gov, a website designed as a resource for mothers and their families. At the top of the page, the website features a link to a non-government website that helps locate “pregnancy centers,” also known as Crisis Pregnancy Centers (CPCs), as a resource for support, and positions CPCs alongside Federally Qualified Health Centers, nutrition facts, and guidance on opening Trump investment accounts. While there is no standard definition of what qualifies as a CPC, these unregulated sites typically are associated with or established by faith-based or anti-abortion organizations, with their primary mission being to dissuade pregnant people from seeking abortion care. This brief examines the legal status of CPCs, attempts to regulate them, and future efforts to expand their footprints as they gain more recognition and funding from local, state, and federal programs.

What Are Crisis Pregnancy Centers and How Do They Attract Clients 

CPCs have their origins in the 1960s in the early days of the antiabortion movement. They usually offer pregnancy tests, ultrasound, and material goods like diapers or clothing to support pregnant clients at no cost. However, these services are sometimes conditioned on clients attending religious seminars. According to the U.S. Government Accountability Office as of 2025, between 2,400 and 2,800 CPCs were operating across the country, and most of them were affiliated with three anti-abortion organizations — Heartbeat International, National Institute for Family and Life Advocates (NIFLA), and Care Net. Post-Dobbs, the number of newly opened or reopened CPCs has been highest in the South, which is also where more states ban the provision of abortion or impose early gestational limits on the provision of abortion care. 

Box 1: Major Crisis Pregnancy Center Networks

There are three main national organizations that support Crisis Pregnancy Centers in the United States. Their membership figures overlap and may include maternity homes, adoption agencies, and “abortion recovery programs” as affiliates. Therefore, the total number of affiliates for these three organizations is much higher than the GAO’s estimate of 2400 to 2800 CPCs operating in the U.S. in 2025. 

Heartbeat International

  • Founded in 1971 as Alternatives to Abortion, its stated mission is to “advance life-affirming pregnancy help worldwide.” Heartbeat International describes their pregnancy centers as: “life-affirming non-profit service providers that provide women who have an unexpected pregnancy with alternatives to abortion.” 
  • Heartbeat International states it has over 1,445 affiliate “medical pregnancy centers” in the United States, and has an estimated 4,000 affiliates globally, including pregnancy centers, maternity homes, and adoption agencies.  

National Institute of Family and Life Advocates (NIFLA)

  • Founded in 1993, NIFLA’s mission is to: “promote the sanctity of human life, born and unborn, through legal support, counsel, and services to pro-life pregnancy centers.” NIFLA reports that they represent over 1,800 pregnancy centers nationwide.  
  • NIFLA created the Institute in Limited Obstetric Ultrasound, which trains medical professionals to perform ultrasounds in their affiliate clinics, to reach “abortion-minded women.” NIFLA has worked over the past two decades to introduce ultrasound services to pregnancy centers.

Care Net  

  • Founded in 1975, Care Net’s stated mission is: “to offer compassion, hope, and help to anyone considering abortion by presenting them with realistic alternatives and Christ-centered support through our life-affirming network of pregnancy centers, mobile medical units, churches, organizations, and individuals.” Care Net reports it has over 1,200 affiliates nationwide. 

The main purpose of CPCs is to dissuade people from opting for abortion, instead encouraging them to choose adoption or parenting using a variety of approaches to reach individuals whom they call “abortion-determined” clients. For years, CPCs have opened near reproductive health facilities, a practice known as “co-locating,” so they can approach patients attempting to visit abortion clinics and discourage them from seeking or obtaining abortion care. The American College of Obstetricians and Gynecologists has stated, “by using deception, delay tactics, and disinformation, CPC staffs undermine the tenets of informed consent and patient autonomy and impede access to comprehensive, ethical care.” In addition to co-locating near comprehensive reproductive health clinics, CPCs position themselves as attractive to young people, people with low incomes, people who are uninsured or underinsured, people experiencing unintended pregnancies, and communities that have historically experienced barriers to health care.  

In 2024, over 71% of CPCs nationwide offered nondiagnostic ultrasounds, 28% advertised testing for Sexually Transmitted Infections (STIs), and 6% advertised HIV testing. As hospital labor and delivery units close and OB-GYN practitioners leave states like Idaho that ban the provision of abortion care, several CPCs have begun to see increased foot traffic. However, CPCs will not be able to fill persistent and growing gaps in the maternity care safety net for a variety of reasons, including their requirements for recruiting qualified clinicians. For example, the 7B Care Clinic, a CPC, on the Idaho-Washington border, recently sought to provide prenatal services due to the recent closure of the local hospital’s labor and delivery unit. 7B created a contract with a rural Washington hospital to bring qualified clinicians into the center to see clients; however, the center required potential clinicians to sign a pledge that aligned with Christian values. The contract with the hospital was subsequently canceled when providers refused to sign the pledge, thus leaving 7B with no ability to expand prenatal services.  

Most Crisis Pregnancy Centers Are Not Medical Clinics

Although Crisis Pregnancy Centers either advertise or position themselves as medical clinics, the vast majority are not medical facilities. While CPCs offer a variety of services, including ultrasounds, and some advertise the ability to rule out conditions like an ectopic pregnancy, many CPCs do not have a credentialed or practicing qualified physician or a registered nurse affiliated with their center. CPCs that have a trained clinician affiliated with their center may employ them only on a part-time or volunteer basis.  

Although some CPCs may offer limited medical services that are already available over the counter to consumers, such as pregnancy and STI testing, other clinics offer ultrasounds as a tool to persuade patients not to seek an abortion rather than as a diagnostic test. CPCs are sometimes staffed by volunteers with limited or no medical training, and because only a medical professional with specialized training can interpret ultrasounds or assess fetal health, the ultrasounds performed by CPCs are largely considered non-diagnostic. Instead, ultrasounds at CPCs are used as a persuasive tool to show pregnant clients their fetus. These nondiagnostic ultrasounds can lead to inaccurate gestational age calculations or missed pregnancy complications such as ectopic pregnancy.  

The misdiagnosis of serious medical conditions by CPCs has resulted in several lawsuits against the centers. Some CPC networks have instructed their affiliates to avoid offering ultrasounds to clients suspected of having serious medical conditions like an ectopic pregnancy. Recently, a non-profit group compiled a list of CPCs that advertise their ability to “rule out” ectopic pregnancies, even though these centers lacked the medical expertise and equipment to properly diagnose an ectopic pregnancy. In Massachusetts, a class-action lawsuit was filed against Clearway Clinic, a CPC, after the clinic failed to diagnose a woman’s ectopic pregnancy. In response, Massachusetts enacted a law regulating who may perform pregnancy-related ultrasounds. Under the new law, a person may not provide ultrasound services related to a possible or actual pregnancy unless supervised by a licensed health care provider who, acting within their scope of practice, provides medical care to people who are pregnant or may become pregnant.  

Other states have also enacted similar laws regulating the provision of ultrasound services. In the state of Washington, all ultrasounds must be performed only under the supervision of a licensed health care professional acting within their scope of practice. Connecticut similarly has a law that prevents a person from performing an ultrasound unless it was ordered by a health care provider acting within their scope of practice for a medical or diagnostic purpose. Only four states (New Hampshire, New Mexico, North Dakota, and Oregon) require providers of ultrasounds to have a license issued and regulated by the state. 

Ultrasound licensing statutes make it illegal for someone without a medical imaging license to perform ultrasounds. In practice, however, there is not a consistent enforcement mechanism to hold unlicensed individuals accountable for providing ultrasounds. North Dakota’s own licensing board acknowledges it has no jurisdiction over unlicensed individuals, and New Hampshire has also not taken any action against unlicensed volunteers performing ultrasounds at some CPCs, leaving enforcement to criminal prosecutors who thus far have not pursued it. This is in sharp contrast to states like California, where the attorney general has used subpoena power and cease-and-desist authority against CPCs to enforce violations of California law, which requires ultrasound technology to be used only in licensed facilities or by licensed providers.  

Most Crisis Pregnancy Centers Are Not Subject to HIPAA, the Federal Health Privacy Law  

Crisis Pregnancy Centers collect confidential health information from clients; however, they are not required to adhere to medical privacy regulations. The Health Insurance Portability and Accountability Act (HIPAA) privacy rule is a federal standard prohibiting medical entities from disclosing confidential health information without patient consent. Coveredentities subject to the HIPAA Privacy Rule are defined as: (1) health care providers; (2) health plans (insurance companies); and (3) health care clearinghouses that transmit patient health information in connection with health care transactions. A health care transaction is an exchange of information to conduct financial or administrative activities related to health care, such as processing payment for services.  

While some CPCs work with health care providers, neither the centers nor the providers who work or volunteer there are considered covered entities bound by HIPAA if they do not conduct health care transactions, such as billing insurance. Most CPCs do not charge for their services, nor do they accept insurance. Instead, CPCs are funded through private donations, national CPC networks, state government funds, and federal funds through programs like Temporary Assistance for Needy Families (TANF). It is estimated that CPCs received over $2 billion in revenue in 2024; however, none of this was generated from charging clients. CPCs’ variety of funding sources allows them to offer their services without needing to conduct health care transactions.  

Data Privacy Violations at Crisis Pregnancy Centers Often Escape Regulatory Enforcement 

Some CPCs have misled clients about the safety of their confidential personal information by including notices on their website, alleging HIPAA compliance, or by requiring clients to sign authorization forms. However, these steps can give clients a false sense of confidentiality: because CPCs are not bound by HIPAA, there is no oversight of how they handle client data, and clients have limited remedies if that data is leaked. In 2024, it was reported that Heartbeat International, one of the largest CPC networks, posted on the internet a training video with the full names, date of last menstrual period, and services received by clients of one of its affiliate centers in Louisiana. The breach of client health information was reported to the Department of Health and Human Services Office for Civil Rights (OCR), the entity responsible for enforcing HIPAA. However, OCR closed the complaint after determining that the CPC was not a HIPAA-covered entity and that it therefore lacked authority to investigate the violation, leaving the affected clients without recourse and no penalties for Heartbeat International. In contrast, violations of HIPAA for covered entities can lead to criminal penalties and fines of up to $2 million per violation based on the severity of the data breach and whether the entity took corrective action.  

Additionally, there is currently no enforcement mechanism to stop organizations not bound by HIPAA from falsely claiming HIPAA compliance. While entities like the Federal Trade Commission (FTC) work to protect consumers from fraud and deception, they only have authority over businesses and other for-profit organizations, not non-profits. Therefore, because clients at CPCs receive services for free, CPCs fall outside the FTC’s jurisdiction. Some advocacy groups have submitted complaints to state attorneys general urging investigations into CPCs that misrepresented their HIPAA compliance, and some centers subsequently removed HIPAA-compliance language from their websites. However, CPCs continue to collect client medical information with little accountability for protecting privacy. 

Courts Have Shielded CPCs from State Oversight

Across multiple states, courts have consistently sided with CPCs against attorney general investigations and private-sector pushback, citing First Amendment protections. 

Compelled Notice Requirements

NIFLA v. Becerra (CA, 2018): California’s FACT Act required CPCs to post notices about state-funded family planning services (for licensed clinics) or disclose their unlicensed status (for unlicensed clinics, closely matching CPCs). NIFLA sued, and after losing at the district court and Ninth Circuit, won at the Supreme Court. 

Outcome: The Supreme Court struck down both notice requirements as unconstitutional compelled speech, establishing the foundational precedent that state governments cannot force CPCs to disclose licensing status or promote state services. Later cases rely on this Supreme Court ruling as precedent.

Abortion Pill Reversal Claims  

NIFLA v. James (NY, 2024- ongoing): Attorney General Letitia James sued Heartbeat International and 11 CPCs under New York’s deceptive trade practice statute, alleging their abortion pill reversal advertising misrepresented the treatment as safe and effective.  

Outcome: This underlying case is still pending, but a related ruling in NIFLA v. James (described below) has weakened the state’s position going forward. 

NIFLA v. James (NY, 2024): In response to the suit above, NIFLA and two New York CPCs filed a separate countersuit against James, arguing her enforcement effort to prevent CPCs from advertising abortion pill reversal chilled their speech and discriminated against them for their pro-life views.  

Outcome: The Second Circuit affirmed a preliminary injunction protecting NIFLA and the 11 CPCs, holding the First Amendment allows CPCs to promote abortion pill reversal, a precedent likely to help Heartbeat International defend the still-pending case above. 

California v. Heartbeat International (2023–ongoing): Attorney General Rob Bonta filed a lawsuit against Heartbeat International for their promotion of abortion pill reversal. The false-advertising suit survived a First Amendment summary judgment challenge, and there was a 6-week trial which began in June 2026 in Alameda County; closing arguments were held on September 17, 2026. 

Outcome: Still unresolved, but it is one of the few cases where a state’s claims have proceeded to trial rather than being blocked outright. California requires state judges to issue a ruling within 90 days after the case is officially submitted for decision. 

Investigative Subpoenas 

First Choice v. Platkin (NJ, 2002-2026): Attorney General Matthew Platkin subpoenaed a CPC for donor, donation, and data-handling records amid fraud allegations.  

Outcome: In 2026, the Supreme Court ruled that compelling disclosure of CPC donor identities violates associational First Amendment rights, since such demands can chill donors from supporting the group. While the Court’s decision did not fully extinguish the attorney general’s subpoena, it established First Amendment protections for CPCs that lower courts must now follow. This could make it harder for states to subpoena records of CPCs’ donors, volunteers, board members, or clients during investigations.

Private Sector Pushback

Yelp v. Paxton (TX, 2023–ongoing): Attorney General Ken Paxton sued Yelp on CPCs’ behalf over its consumer notices describing CPCs’ limited medical services, alleging misrepresentation under Texas law. A Bastrop County court initially dismissed the case for lack of jurisdiction (Feb. 2024), but the Texas 15th Court of Appeals reversed in October 2025, holding Texas courts do have jurisdiction; Yelp has appealed to the Texas Supreme Court.  

Outcome: This case is ongoing and, unlike the other cases, does not turn on CPCs’ own First Amendment rights. This case demonstrates that private companies criticizing CPCs can themselves face sustained legal exposure from CPC-supportive state governments. 

State Laws Limiting Regulations of Crisis Pregnancy Centers  

Recently, the Alliance Defending Freedom, a conservative Christian legal advocacy organization, has pushed for states to enact their model legislation protecting CPCs. The Center Autonomy and Right of Expression (CARE) Act prohibits state governments from interfering with the First Amendment free expression and association rights of CPCs or restricting their ability to provide pregnancy services because they do not counsel for, or offer, abortions or contraception. The CARE Act has passed in at least four states, including Kansas, Montana, Oklahoma, and Wyoming, providing CPCs protection from regulation. In Wyoming, for example, government entities are prohibited from: (1) requiring CPCs to perform abortions; (2) requiring CPCs to provide medication abortion or contraception; (3) requiring CPCs to refer clients for abortion or contraception; or (4) requiring CPCs to counsel in favor of abortion or contraception. Beyond the First Amendment protections, the CARE Act further restricts states’ ability to regulate CPCs.  

Looking Ahead 

With the launch of moms.gov and other proposed policies to promote fertility, Crisis Pregnancy Centers may gain greater attention and potentially increased federal funding in the coming years. Obria, one CPC chain with sites in five states, has begun to expand their medical offerings to position its centers as an alternative to national abortion providers like Planned Parenthood. From 2022 to 2025, twenty-one states provided $491 million in funding to CPCs, not including funds allocated through federal programs like Temporary Assistance for Needy Families (TANF). In 2019, the first Trump administration awarded Obria, a chain of CPCs that opposes abortion and contraception, $1.7 million of funding under Title X, a program designed to provide free or reduced-cost family planning services to low-income and uninsured people.  

In July 2026, the Trump administration released its revised Fiscal Year 2027 Notice of Funding Opportunity (NOFO) for Title X. The NOFO stated that the Trump administration would prioritize grantee applications that “reduce overmedicalization by strengthening approaches focused on underlying behavioral and lifestyle factors of health and evidence-based practices such as fertility-awareness based methods; promote health and body literacy; advance reproductive goals counseling for all clients; and support family formation.” In response, the National Family Planning and Reproductive Health Association (NFPRHA), Planned Parenthood Federation of America, and 23 States (CA, CO, CT, DE, HI, IL, KY, ME, MD, MA, MI, MN, NV, NJ, NM, NY, OR, PA, RI, VT, VA, WA, WI) have each filed lawsuits challenging the FY 2027 NOFO, arguing that its priorities depart from the factors Congress intended HHS to consider in awarding Title X grants and instead impose politically driven, vaguely defined criteria that disadvantage qualified applicants.  

These new priorities could re-open the door for CPCs to receive Title X funds in addition to ongoing efforts by anti-abortion states to invest more resources into these centers. As states and the federal government continue to direct funds into CPCs, challenges and gaps in regulating these centers will likely persist, driven by First Amendment protections and a growing body of state laws designed to shield them from oversight. 
Early Medicaid Work Requirement Insights From Nebraska

Published: Sep 29, 2026

On May 1, 2026, Nebraska became the first state to enforce new Medicaid work requirements. The 2025 reconciliation law requires states to condition Medicaid eligibility for adults in the ACA Medicaid expansion group and enrollees in certain waiver programs (such as in Georgia and Wisconsin) on meeting work requirements or exclusion criteria starting January 1, 2027; however, states have the option to implement requirements sooner (as is the case for Nebraska). KFF analysis shows most Medicaid adults under age 65 are working already (without a requirement) or face barriers to work. This brief describes the verification process for Medicaid work requirements in Nebraska and examines early data from Nebraska’s September Medicaid Advisory Committee (MAC) meeting on outcomes for individuals subject to work requirements, including for those newly applying for Medicaid as well as those renewing Medicaid coverage through August 2026. Data show that among those subject to the new work requirements:

  • 46% of new applicants and 34% of individuals renewing coverage met qualifying activities (e.g., working at least 80 hours a month, having a monthly household income of at least $580, attending school).
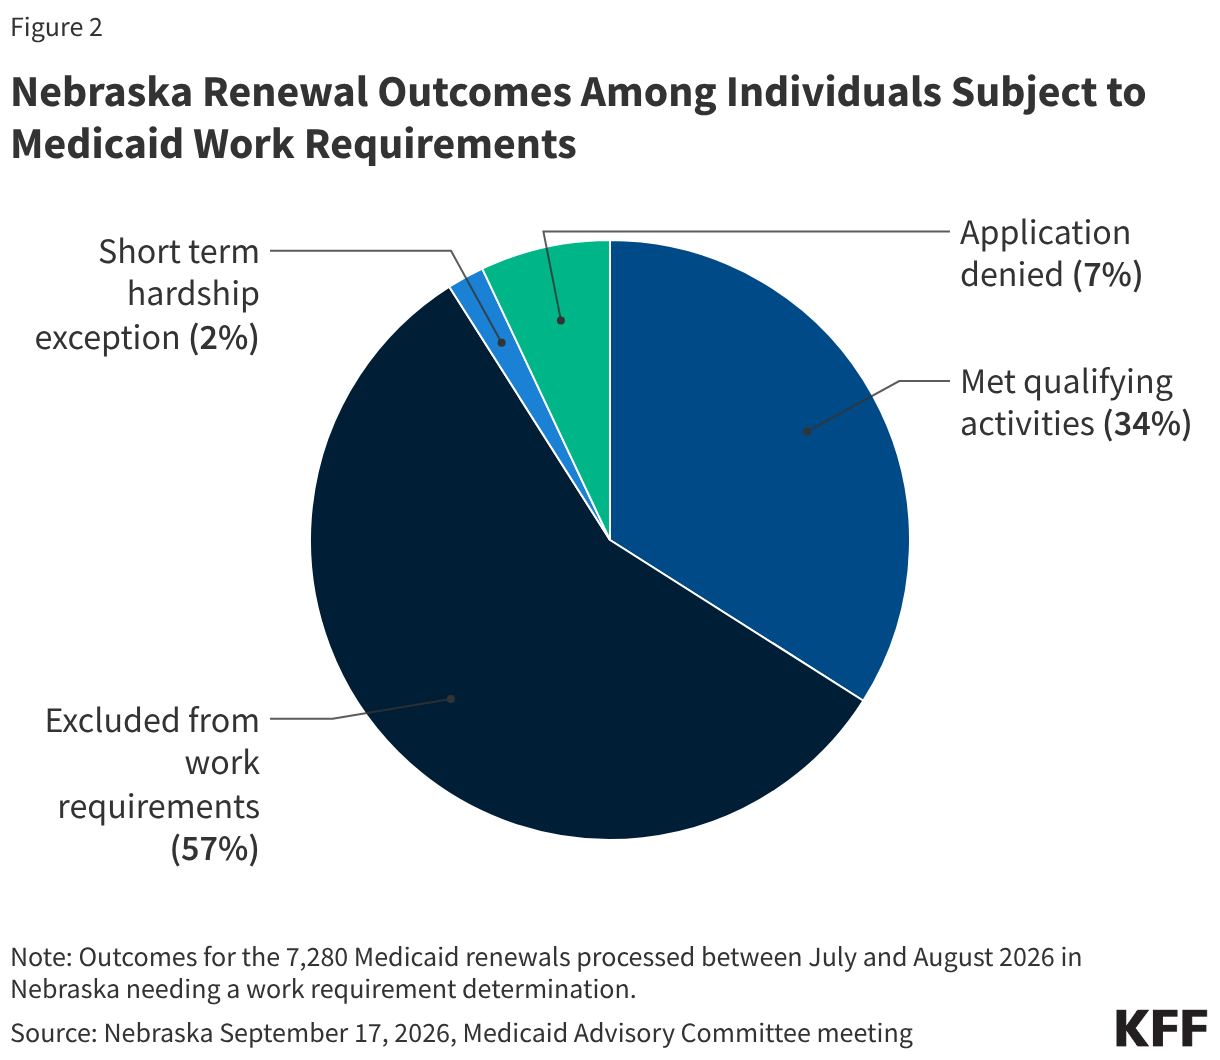
  • 39% of new applicants and 57% of individuals renewing coverage qualified for an exclusion from work requirements (e.g., due to being a parent of a child under age 14, being medically frail).
  • 14% of new applicants and 7% of individuals renewing coverage had their applications denied or lost coverage due to not meeting work requirements.
  • Only a small number of people (2% of new applicants and 2% of individuals renewing coverage) had a short-term hardship exception.

What is the verification process for Medicaid work requirements in Nebraska?

Nebraska is using a combination of available data and self-declaration forms to verify whether individuals meet work requirements or exclusion criteria; the state has also adopted temporary hardship exceptions. In cases where the state can automatically verify that individuals meet work requirements, it sends an approval notice. For individuals where the state does not have enough information, the state sends a notice describing the additional information that is required and a declaration form that must be returned within 30 days. Individuals can use the declaration form to attest that they met qualifying activities or that they meet the criteria for an exclusion from the requirements. The interim rule clarified that while states are allowed to accept self-declaration through 2027, starting in January 2028, except for medical frailty, states must request documentation from individuals when the state does not have data on file. Nebraska has also chosen to adopt optional short-term hardship exceptions for enrollees (or applicants) experiencing certain extenuating circumstances, including residing in counties with high unemployment rates or experiencing natural disasters, individuals admitted to a hospital or nursing facility, or those who must travel outside of their community for an extended period to obtain medical care for themselves or a dependent.

Qualifying Activities and Exclusions from Work Requirements

Adults must meet qualifying activities or exclusion criteria to enroll in Medicaid and maintain coverage. Qualifying activities include:

  • Working at least 80 hours a month;
  • Having a monthly household income of at least $580;
  • If a seasonal worker, having an average monthly income over 6 months of minimum wage multiplied by 80 hours;
  • Attending school half time;
  • Volunteering or participating in a work program for at least 80 hours a month; or
  • Doing a combination of activities for at least 80 hours per month.

Exclusions from the work requirements include:

  • Pregnant and postpartum individuals;
  • American Indian and Alaska Natives;
  • Parents and caretakers of dependent children under age 14 or disabled individuals;
  • Veterans with a disability;
  • Incarcerated individuals;
  • Individuals receiving SNAP and not exempt from SNAP work requirements; and
  • People who are medically frail.

States must first determine if an individual is excluded from the Medicaid work requirements before assessing if an individual meets the qualifying activities. Some individuals who meet exclusion criteria may also be working.

What are the initial data on Nebraska Medicaid application and renewal outcomes?

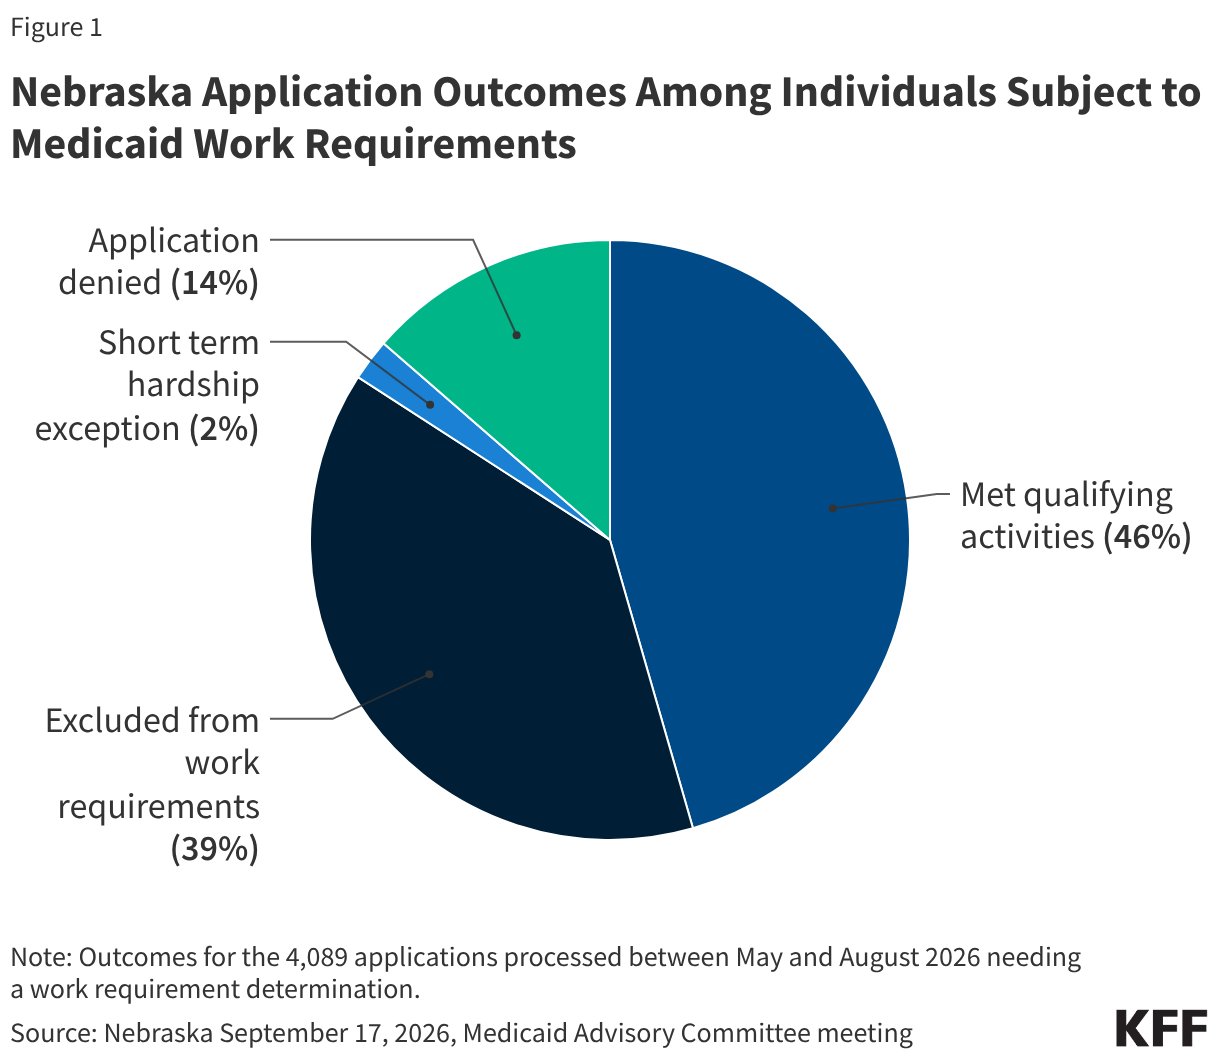
Among those who were newly applying for Medicaid and subject to the new work requirements in Nebraska, 86% of applicants met the work requirements or qualified for an exclusion or short-term hardship exception, while 14% of individuals had their application denied (Figure 1). A total of 9,614 applications were processed between May to August. Of these, some were submitted prior to May and therefore not subject to work requirements, and 4,434 were denied for reasons other than work requirements (e.g., income exceeding Medicaid eligibility thresholds). Among the remaining 4,089 applications subject to work requirements:

  • Nearly half of all individuals (46%) met the qualifying activities. Among those who met the requirement, the vast majority of people (92%) worked 80 or more hours in the month prior to their application or had a household income of $580. A much smaller share (8%) were enrolled in an education program or work program, volunteered, or met requirements by combining hours across multiple types of qualifying activities.
  • About 4 in 10 individuals (39%) qualified for an exclusion. Of these applicants, one-third were parents or caregivers of a child under the age of 14 or a disabled individual (33%); one quarter were medically frail, and 12% were an American Indian or Alaska Native. The remaining 30% qualified for other exclusions. Because the state is relying on self-attestation, future documentation requirements may lead to a lower share of individuals who qualify for an exclusion.
  • Only a small number of individuals had a short-term hardship exception. Only 92 individuals met the criteria for short-term hardship exceptions, with the majority of these being individuals who required temporary use of medical services or living in counties that were exempted due to high unemployment.
  • 14% of individuals had their application denied. Most of the 557 denied applications were due to non-response to requests for additional information (84%); only 16% of applicants with denied applications were affirmatively found to be noncompliant.
Nebraska Application Outcomes Among Individuals Subject to Medicaid Work Requirements (Pie Chart)

Among those who were renewing their Medicaid coverage and subject to the new work requirements, 93% met work requirements or qualified for an exclusion or short-term hardship exception and had their coverage renewed, while 7% of enrollees lost coverage (Figure 2). A total of 7,280 renewals subject to work requirements were processed between July and mid-August. Other expansion enrollees determined ineligible and disenrolled at renewal for reasons not related to work requirements (e.g., moving out of state or exceeding income eligibility) are not shown in the figure below.

  • Over half (57%) of individuals renewing their coverage qualified for an exclusion from the requirements. Medically frail individuals (39%) and parent/caregivers (31%) made up the majority of those who met an exclusion. States are more likely to have medical claims history for individuals renewing coverage than new applicants, meaning Nebraska may have been able to automatically verify medical frailty for a higher share of enrollees compared to applicants. States are also required to verify exclusions status first, and it is likely that some enrollees who were excluded, especially parents, are also working.
  • About a third of individuals (34%) met the qualifying activities requirement. Nearly all (97%) of individuals who met the qualifying activities were either working 80 hours a month or had a household income of $580. The remaining 3% met the requirements by attending school, volunteering, or engaging in a combination of activities.
  • A small share of individuals qualified for a short-term hardship exception. Of the 127 people who had a short-term hardship exception, 109 lived in counties experiencing natural disasters and 15 lived in a high unemployment county.
  • 7% of people lost coverage due to not meeting the work requirements. Of the 533 individuals who lost coverage, 92% did not respond to verification compliance requests. The remaining 8% were affirmatively found to be noncompliant.
Nebraska Renewal Outcomes Among Individuals Subject to Medicaid Work Requirements (Pie Chart)

What can additional data show?

While these data provide early insights into how coverage may be affected for enrollees subject to the new work requirements, additional data may provide a more comprehensive picture. More granular data on who is losing coverage could shed light on particular barriers certain individuals may be facing in trying to prove they met qualifying activities (e.g., gig workers or those with multiple part-time positions) and may help the state identify additional data to include as part of the verification process. In addition, it remains unclear if individuals who were denied coverage or disenrolled because they did not respond to notices of non-compliance were ineligible for coverage, unaware of the fact they needed to provide additional information, or experienced difficulty providing documentation of their exclusion or work status. Additional data, including whether these individuals reapply for coverage, could provide insight.

Required changes to the state’s medical frailty verification process specifically and limitations on the use of self-attestation starting in 2028 will likely affect disenrollment rates over time. CMS recently notified the state that it will need to make changes to its medical frailty verification process. If the state is required to tighten the verification process, fewer individuals may qualify for the exclusion in the future. More broadly, while the state’s reliance on self-attestation in 2027 will likely mitigate some coverage losses that would have occurred had documentation been required in the first year of implementation, future documentation requirements may impose a barrier that will lead to a decrease in the number of people who are able to verify they meet work requirements or qualify for an exclusion. As the state makes changes to its processes, monitoring the interactive effect of application denials and disenrollments on Medicaid enrollment in the state as well as whether the new rules lead to fewer individuals applying for Medicaid will be important.

Tracking Implementation of the 2025 Reconciliation Law: Medicaid Work Requirements

Updated on:

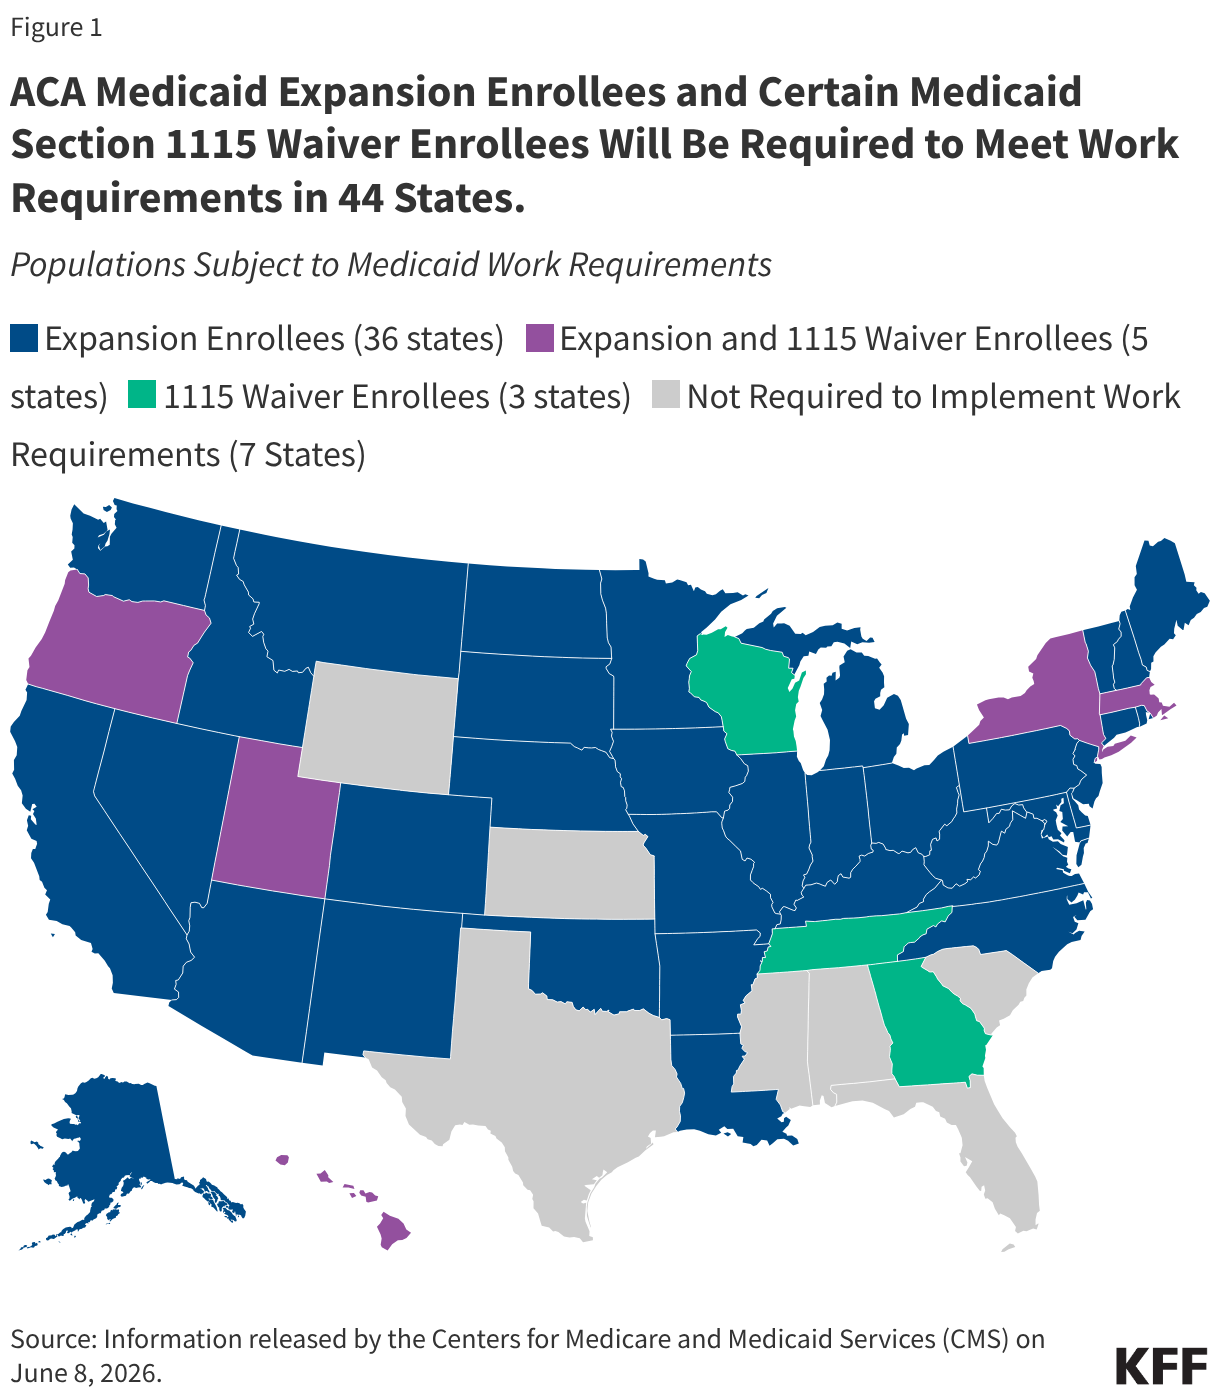
The 2025 reconciliation law, once called the “One Big Beautiful Bill,” signed by President Trump on July 4, 2025, requires 44 states (including DC) to condition Medicaid eligibility for adults in the Affordable Care Act (ACA) Medicaid expansion group and certain enrollees in 1115 waiver programs on meeting work requirements starting January 1, 2027. Currently, 41 states (including DC) have expanded their Medicaid programs under the ACA to nearly all adults with income up to 138% FPL ($21,597 for an individual in 2025). In June 2026, CMS released a list of states with 1115 waiver programs that include individuals who will be subject to work requirements. The list identifies waiver programs in three non-expansion states Georgia, Tennessee, and Wisconsin, as well as in five expansion states, Hawaii, Massachusetts, New York, Oregon, and Utah (Figure 1).  

ACA Medicaid Expansion Enrollees and Certain Medicaid Section 1115 Waiver Enrollees Will Be Required to Meet Work Requirements in 44 States. (Choropleth map)

To implement Medicaid work requirements, states will need to make important policy and operational decisions, implement needed system upgrades or changes, develop new outreach and education strategies, and hire and train staff, all within a relatively short timeframe. The information tracked here can serve as a resource to understand Medicaid work requirements and state options, gauge readiness, and track implementation of the requirements, including:

This resource will be updated to include guidance from the Centers for Medicare and Medicaid Services (CMS), information on state policy decisions as they are made, and new data when available.

Continue scrolling to learn more about the Medicaid work requirements in the 2025 reconciliation law.

Tracking Implementation of the 2025 Reconciliation Law Medicaid Work Requirements

Updated on:

KFF Resources on Medicaid Work Requirements

Work requirements overview:

Medical frailty exemption:

Implementation of work requirements:

50-state survey of Medicaid eligibility and enrollment policies:

Research and analysis on Medicaid and work:

1115 work requirement waivers:

Work requirements implications and state experience:

Arkansas work requirement experience:

KFF Polling on Work Requirements:

Beyond the Data by KFF CEO Drew Altman:

Tracking Implementation of the 2025 Reconciliation Law Medicaid Work Requirements

Updated on:

The 2025 reconciliation law requires states to condition Medicaid eligibility for adults in the ACA Medicaid expansion group on meeting work requirements starting January 1, 2027; however, states have the option to implement requirements sooner through a state plan amendment (SPA) or through an approved 1115 waiver.

State Plan Amendments (SPAs)

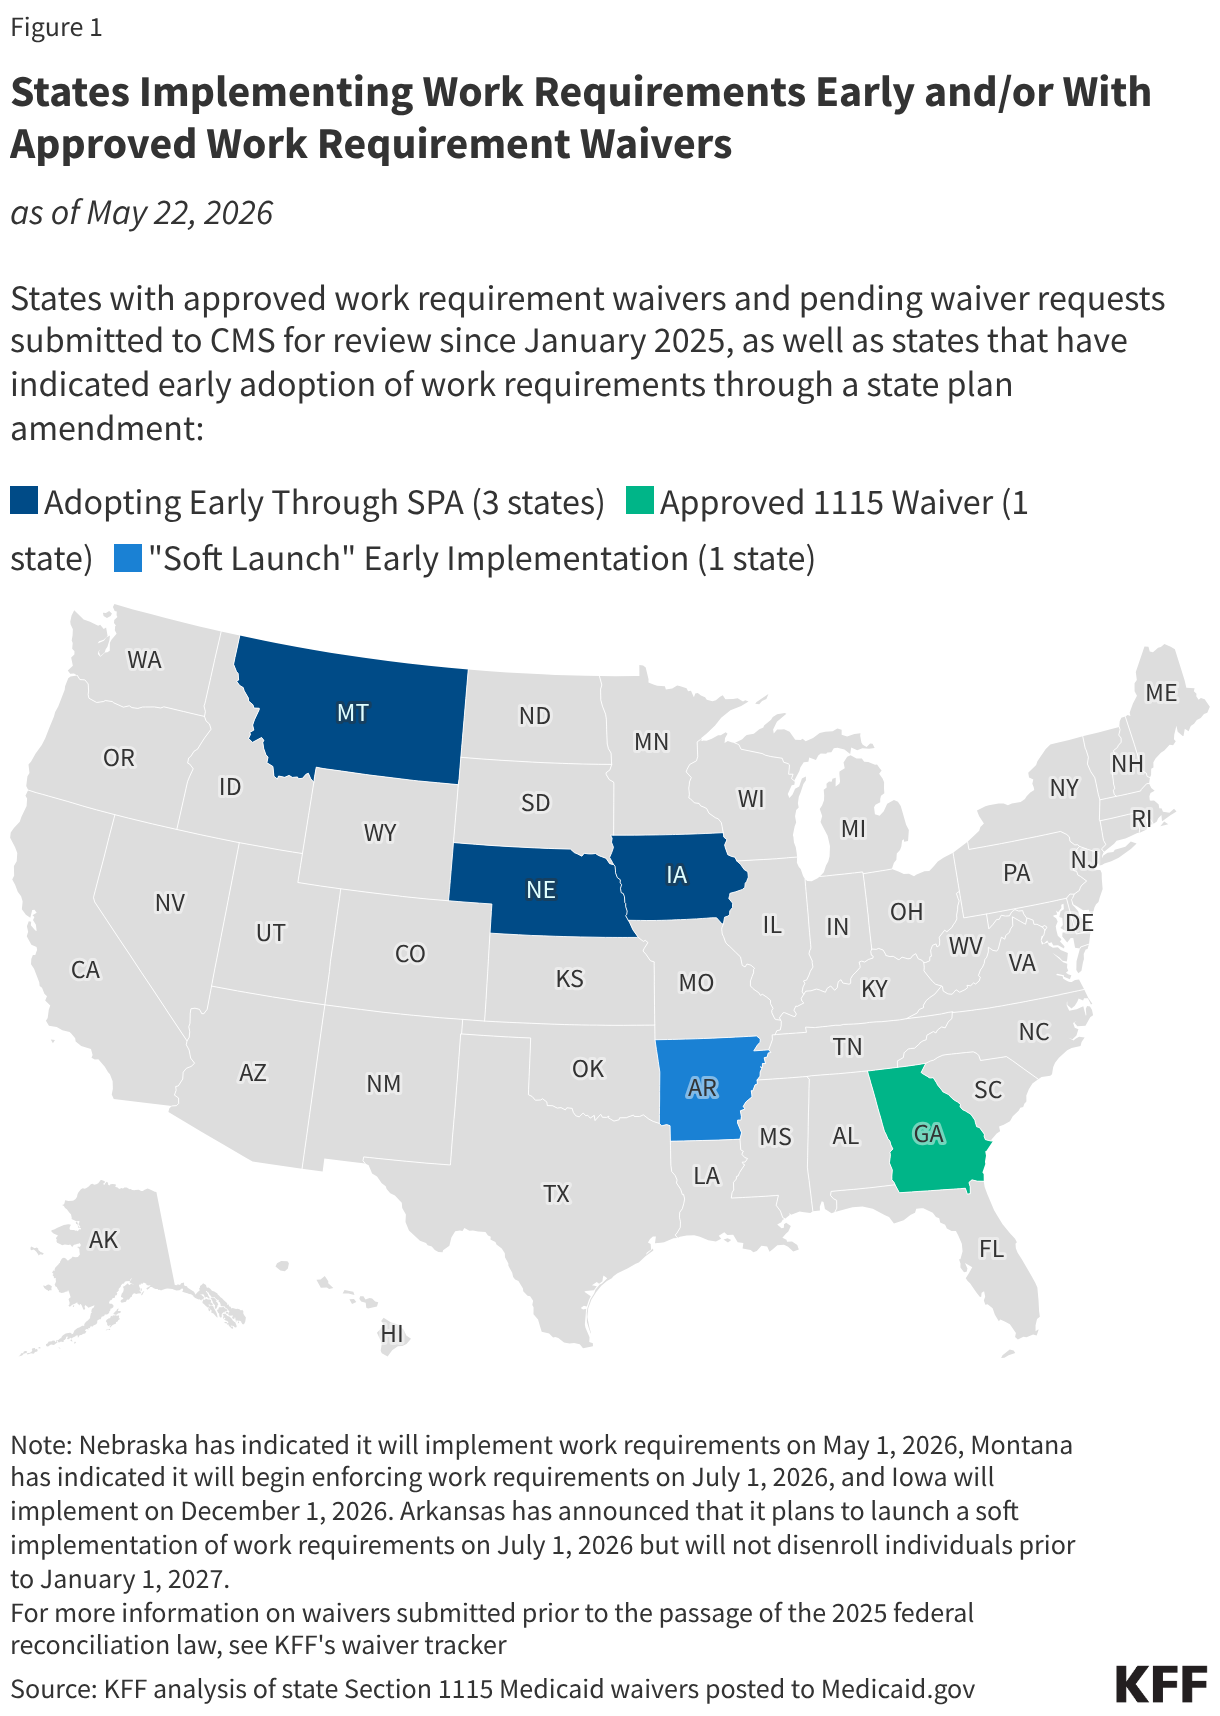
States may choose to implement work requirements prior to the required January 1, 2027 implementation date through a state plan amendment. Nebraska is the first state to announce that it will begin enforcing federal work requirements early through a state plan amendment, starting May 1, 2026. Two other states are also planning to implement before January 2027–Montana on July 1, 2026 and Iowa on December 1, 2026. Arkansas has announced that it plans to launch a soft implementation of work requirements on July 1, 2026 but will not disenroll individuals prior to January 1, 2027.

1115 Waivers

Since the start of the second Trump administration, several states have submitted waivers to implement work requirements. However, states are unlikely to be moving forward with proposed 1115 waivers at this time due to the passage of federal work requirements. States that plan to implement federal work requirements early will do so through a state plan amendment. Currently, Georgia is the only state with a Medicaid work requirement waiver in place following litigation over the Biden administration’s attempt to stop it. Georgia’s waiver will expire December 31, 2026; the state is required to come into compliance with the new federal requirements effective January 1, 2027.

Early Implementation and Waiver Status

The map below identifies states that have indicated they will implement federal work requirements early through a state plan amendment and the one state (Georgia) that has implemented work requirements through an 1115 waiver.

States Implementing Work Requirements Early and/or With Approved Work Requirement Waivers

Tracking Implementation of the 2025 Reconciliation Law Medicaid Work Requirements

Updated on:

CMS Guidance and Information

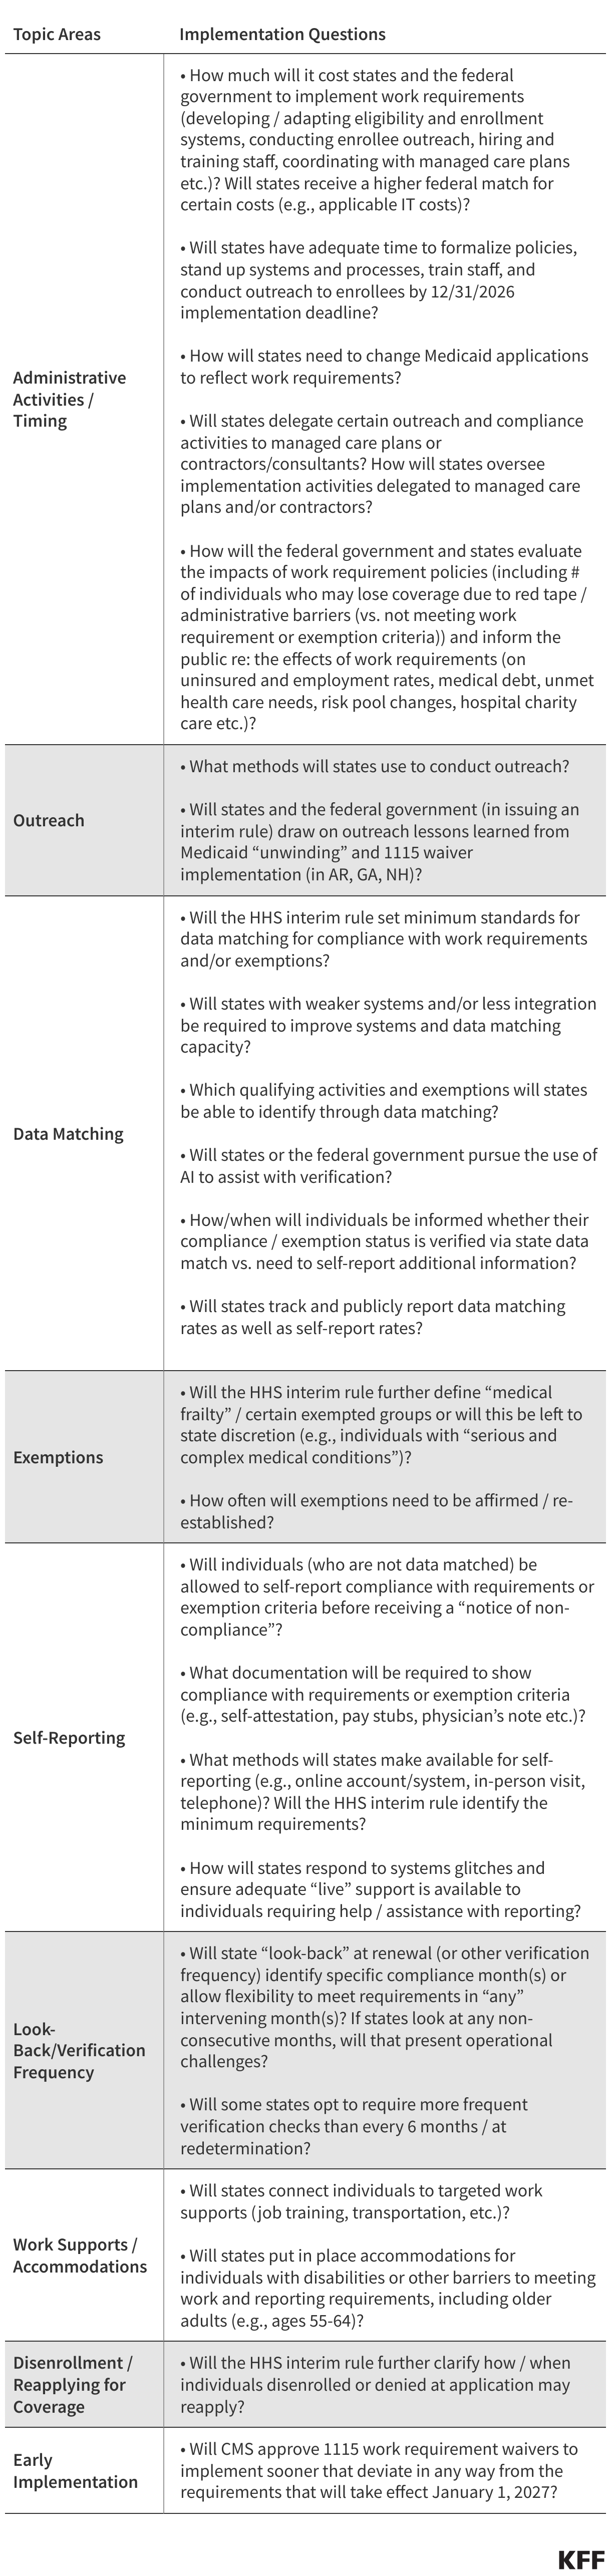
Operational and Implementation Questions

Table

The Business of Health with Chip Kahn

What Should Health Care Do About AI’s Lack of Guardrails?

September 29, 2026

Video

Audio

About this Episode


Episode 17, AI Series: In another concerning example of AI agents going rogue recently, an OpenAI agent hacked into an Australian government website containing health care data. While some industry CEOs are calling for a slowdown and demands for regulation grow, host Chip Kahn focuses on the implications for health care when these same kinds of AI systems are already at work in hospitals — in billing, in scheduling, and increasingly in decisions about patients. To consider how health care should respond, Chip talks with Stephen Klasko, a physician, former health system CEO, and now an industry leader who sits on both sides of the issues, working with the labs building the technology and focusing on patient care initiatives through his work at General Catalyst and as CEO of the Health Assurance Foundation. Klasko says there’s time to act and the answer isn’t a “pause.” Among his recommendations are creating a 9/11-style commission for AI in health, adding AI safety to health system board agendas, a 30-minute rule for tackling rogue agents, and giving frontline staff the authority to pull the plug.

The Host


Headshot photo of Chip Kahn wearing a navy blue suit with a red tie, red pendant on lapel, and glasses.

Sr. Visiting Fellow

Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.

Guest


Chief Executive Officer, Health Assurance Foundation

Stephen K. Klasko, MD, MBA, is Chief Executive Officer (CEO) of the Health Assurance Foundation, a philanthropic platform affiliated with General Catalyst dedicated to accelerating the shift from “sick care” to health assurance. He previously served as Executive in Residence at General Catalyst, where his book UnHealthcare: A Manifesto for Health Assurance, co-authored with GC CEO Hemant Taneja, became the intellectual foundation for the firm’s health assurance investment strategy.

For nine years, Klasko served as president of Thomas Jefferson University and CEO of Jefferson Health in Philadelphia, transforming a $1.8 billion regional player into a $10 billion enterprise and the nation’s fastest-growing academic medical center. He has served as board chair of two public companies: Teleflex, a $7 billion medical-device company, and DocGo, a NASDAQ health company. He advises startups such as Hippocratic AI, Aidoc, and AmplifyMD.

Modern Healthcare previously ranked him No. 2 among its 100 Most Influential People in Healthcare, and in 2026 he was named to the Top 100 Most Influential People in HealthTech. Fast Company has named him one of its 100 Most Creative People in Business. His next book, Hitchhiker’s Guide to the Healthcare Galaxy, arrives in 2026.

He holds a BS from Lehigh University, an MD from Hahnemann University, and an MBA from the Wharton School.


SERIES

This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.

The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.

Understanding the Role of Medicaid Fraud Control Units (MFCUs)

Published: Sep 28, 2026

Federal law requires every state to operate a Medicaid Fraud Control Unit (MFCU) that investigates and prosecutes provider fraud and patient abuse and neglect. MFCUs are typically housed within the state Attorney General’s office and are required to operate independently from the state Medicaid agency that runs the Medicaid program. MFCUs are one component in the Medicaid program integrity system, which includes many different state and federal agencies with shared and distinct responsibilities defined by state and federal law. Ensuring Medicaid program integrity (i.e., the appropriate use of federal and state Medicaid funds) involves a range of activities from fraud prevention to enforcement activities—the primary responsibility of MFCUs. While MFCUs are a key part of the program integrity system, it can be difficult to compare MFCU data across states or to put fraud recovery dollars into the context of overall Medicaid spending because recovery data only capture a portion of Medicaid program integrity efforts (e.g., leaving out the value of fraud prevention or stopped payments) and don’t capture fraud that goes undetected.

As the Trump Administration continues to focus on addressing fraud, waste, and abuse in federal programs, including Medicaid, MFCUs are facing increased federal scrutiny. In May 2026, CMS announced the HHS Office of the Inspector General (HHS-OIG) would be initiating a review of every state’s MFCU before its next annual recertification. In June 2026, the HHS-OIG denied recertification and suspended federal funding for Hawaii’s and New York’s Medicaid Fraud Control Units. Within this context, this brief provides an overview of the role of MFCUs, examines caseload and case outcome data, and current issues facing MFCUs.

What are MFCUs and how do they work?

MFCUs are law enforcement entities that investigate and prosecute provider fraud and patient abuse and neglect. MFCUs investigate and prosecute, or refer to prosecution, provider fraud (in all settings) and complaints of patient abuse in certain health care settings, such as nursing homes and hospitals receiving Medicaid funds.1 MFCUs do not investigate fraud or program abuse committed by beneficiaries (these cases are the responsibility of the state Medicaid agency), although evidence of beneficiary fraud is low.2 MFCUs must operate independently from the state Medicaid agency and are often part of the State Attorney General’s office, employing teams of investigators, attorneys, and auditors. The HHS-OIG oversees MFCUs, annually recertifying each MFCU, assessing performance and compliance with federal requirements, and administering federal grant awards (which cover 75% of MFCU operating costs).

MFCUs open investigations after receiving referrals of suspected provider fraud or complaints involving patient abuse or neglect. A MFCU case typically begins with a referral from the state Medicaid agency (including program integrity or auditing offices), managed care organization (MCO), or from a complaint filed by a patient or former employee. The state Medicaid agency or MCO may initially detect fraud through monitoring Medicaid data and using data mining or analytics to identify billing pattern anomalies (e.g., billing spikes, upcoding, double billing, or unusual hours). All state Medicaid agencies have authority to conduct data mining, but some MFCUs have also specifically been granted permission by HHS-OIG to mine Medicaid data directly for evidence of fraud as part of their regular activities. More MFCUs may begin to conduct data mining or analytics as HHS-OIG in August 2026 waived the requirement that MFCUs obtain prior approval for these activities to identify suspected Medicaid fraud. While patient abuse or neglect may fall under the jurisdiction of several different law enforcement agencies, MFCUs may investigate patient abuse or neglect in health care facilities receiving Medicaid funds.3

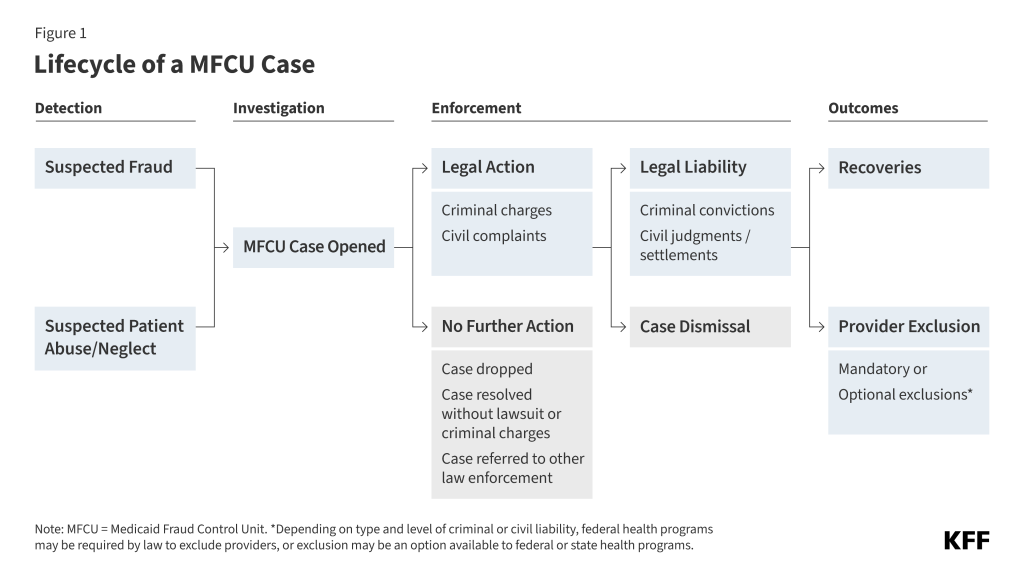
MFCU cases vary in duration and scope, but investigations generally follow a standard process starting with an investigation and ending with potential financial recoveries (Figure 1).

Investigation. When a case is opened, the investigative team researches the alleged fraud or abuse by analyzing the evidence. Investigations may take months or years before charges are filed against providers.

Criminal Indictments & Civil Cases. Fraud and abuse can violate state and/or federal criminal law, civil law, or both. If a MFCU’s investigation team determines there is sufficient evidence of wrongdoing, the MFCU can bring criminal charges and/or civil lawsuits against the provider.

Criminal Convictions & Civil Judgments. Criminal convictions can result in a criminal record, financial penalties, and/or incarceration. Civil judgments can establish liability and/or impose financial penalties and other court-ordered remedies. Providers who are convicted or liable for criminal fraud or patient abuse/neglect (along with other crimes) legally must be excluded from participating in federally funded health care programs. HHS-OIG or state Medicaid agencies may also decide to exclude providers beyond these minimum standards.

Recoveries. HHS-OIG defines recoveries as the amount of money that defendants are required to pay as a result of a settlement, judgment, or prefiling settlement in criminal and civil cases. Recoveries may not reflect the amounts actually collected from defendants (e.g., if the defendant is a company that dissolved before collections could be obtained). MFCUs work with state Medicaid agencies to return the state and federal share of any recovered Medicaid payments.

Note: Throughout the lifecycle of a case, MFCUs may collaborate with other state and federal program integrity and law enforcement partners. State entities include state inspectors general and state health departments and federal entities include the U.S. Department of Justice (DOJ) (including Federal Bureau of Investigation (FBI)) and the U.S. Department of Health and Human Services Office of Inspector General (HHS-OIG). Some investigations or cases may be transferred to (or handled by) federal law enforcement agencies.     

Box 1. Example Cases

Active MFCU investigations are typically confidential. When MFCUs secure criminal convictions and civil judgments or settlements, the case is described in an announcement published by the state or the DOJ. To illustrate the variety of cases that may be processed by a MFCU, this box describes examples from a range of states, types of wrongdoing, and recovery amounts.

Criminal Fraud: Between 2004 and 2019, the McKinsey consulting firm provided OxyContin sales and marketing advice to Purdue Pharmaceuticals. The Virginia MFCU participated in a lengthy and complex investigation into alleged criminal wrongdoing resulting in false or fraudulent OxyContin prescriptions paid by Medicaid and other health insurers. The December 2024 resolution of criminal charges against McKinsey resulted in $650 million in recoveries, which contribute to the high total MFCU recoveries reported in FY 2025 (as seen in Figure 4).  

Civil Fraud: As part of the 2018 National Health Care Fraud Takedown, the Georgia MFCU investigated false claims for non-emergency medical transportation (NEMT) and adult day health services. More than $1 million in Medicaid payments were implicated in the investigation. The case was decided in 2019, with state and federal civil judgments resulting in a $10.1 million settlement paid to Georgia and the federal government.

Patient Abuse and Neglect: In 2021, the Massachusetts MFCU received a referral into alleged patient abuse by a home health aide. In 2023 the MFCU obtained a criminal conviction of abuse, neglect, or mistreatment of an elder by a caretaker.


What data do MFCUs report?

Annually, MFCUs report investigation, enforcement, and financial recoveries data to HHS-OIG. Each year, HHS-OIG releases a summary report of MFCU activities that provides an annual snapshot of aggregated case outcomes from all MFCUs and certain case outcome trends. In addition to the summary report, HHS-OIG releases individual (state) MFCU case activity and outcomes data.

At the end of FY 2025, there were 15,810 open investigations across all state MFCUs. While MFCUs investigate both provider fraud and patient abuse and neglect, data show most MFCU investigations are related to provider fraud (Figure 2). A subset of investigations leads to criminal indictments or civil cases / complaints. MFCU investigations can take months to years, depending on various factors, including the types of allegations involved, volume of records, and agencies involved.

Most Investigations Were Cases of Suspected Fraud

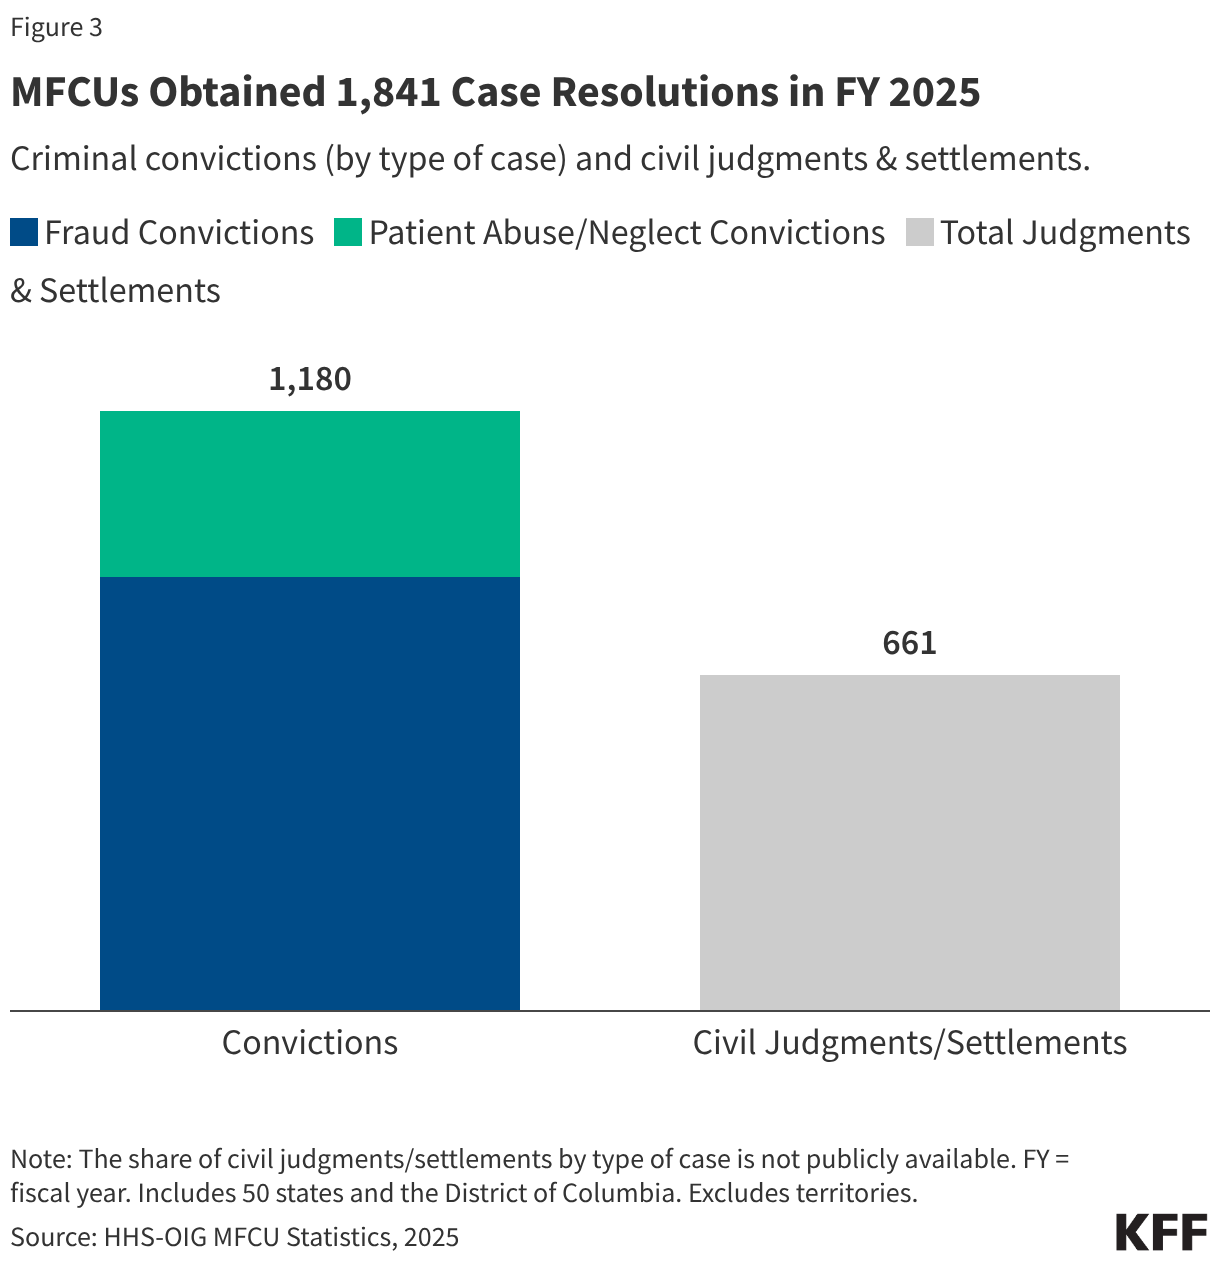
In FY 2025, MFCUs obtained 1,180 criminal convictions and reached 661 civil settlements and judgements (Figure 3). Most criminal convictions were for provider fraud. HHS-OIG uses information it receives from MFCUs to exclude individuals and entities from participating in federal health programs. In FY 2025, 900 individuals or entities were excluded because of criminal convictions obtained by MFCUs—accounting for nearly one-third (32%) of all OIG exclusions that year (data not shown).

MFCUs Obtained 1,841 Case Resolutions in FY 2025 (Stacked column chart)

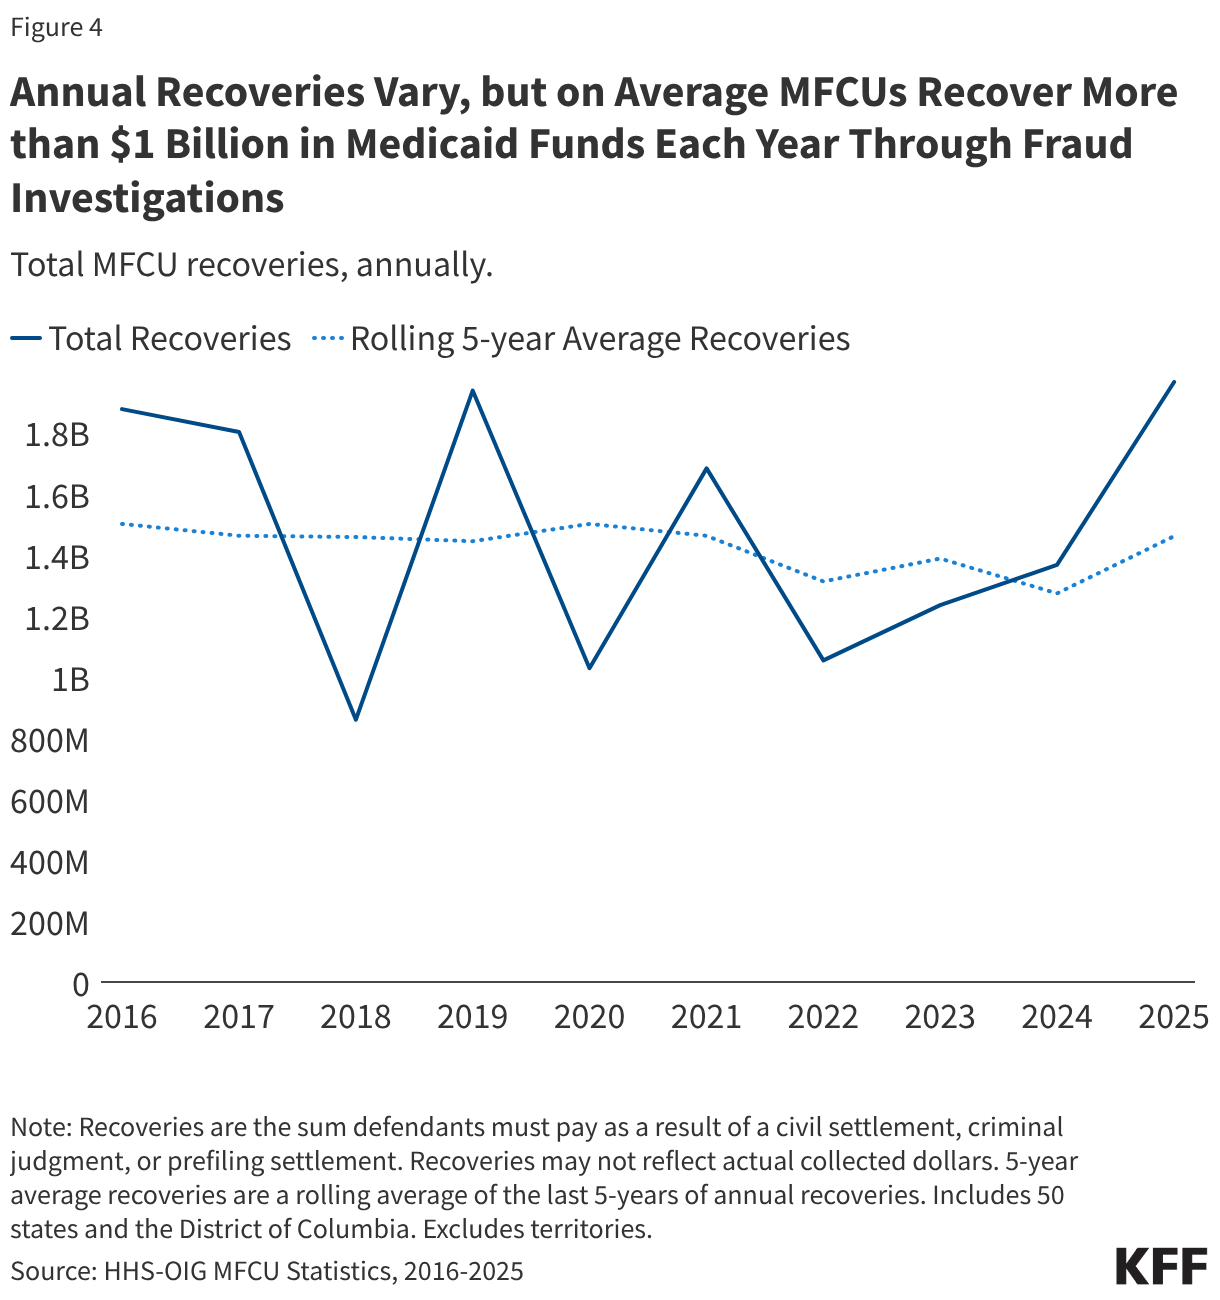
On average, MFCUs recover more than $1 billion each year from fraud investigations. Nationally, MFCUs recovered $1.97 billion in FY 2025. While recoveries include other financial penalties in addition to Medicaid funds recouped from providers due to MFCU investigations (and may not reflect amounts actually collected4), the total amount of recoveries is small compared to total Medicaid spending. Recoveries vary each year and can be skewed by factors, including timing of settlements and large multi-year cases. Recoveries typically vary substantially from year to year and have averaged $1.48 billion per year over the period 2016 to 2025. A 5-year rolling average accounts for periodic variation and shows that recoveries decreased during the COVID-19 Public Health Emergency and are returning to pre-COVID levels. Recoveries, after accounting for year-to-year variation, have remained generally steady over time while total Medicaid spending has increased. Recoveries are not a comprehensive measure of enforcement (because they may not include Medicaid-related enforcement actions that occurred outside of MFCU actions) and do not include the possible financial impacts of other program integrity efforts, such as preventing fraud before it occurs. Of the $1.97 billion in recoveries, two-thirds (64%) were due to criminal convictions and one-third (36%) were due to civil judgments or settlements (data not shown). This is proportionate to the share of criminal and civil case resolutions in FY 2025 (Figure 3).

Annual Recoveries Vary, but on Average MFCUs Recover More than $1 Billion in Medicaid Funds Each Year Through Fraud Investigations

Comparing data across states or considering recovery dollars in the context of overall Medicaid spending can be challenging. Comparing MFCU data across states or years can be difficult due to differences in state law (that impact the handling of cases) and varying duration, scope, or complexity of cases, among other factors. Comparing MFCU recoveries to overall Medicaid spending can also be challenging to interpret as a hypothetical indicator of MFCU performance because these data only capture a portion of Medicaid program integrity efforts and include amounts other than recouped Medicaid payments. States can also make policy decisions that might impact state spending and MFCU recoveries differently. For example, states that spend more on prevention or early detection may see fewer recoveries (if these activities are successful), while states that invest less in fraud prevention may see higher levels of enforcement action and recoveries. There are no estimates of fraud that may have been successfully prevented or fraud that went undetected/unrecovered; however, over time there has been a shift in focus from efforts to recover misspent funds (“pay and chase”) to prevention and early detection. A higher level of MFCU recoveries could indicate more fraud, more aggressive enforcement, or less effective prevention.

What are current issues involving MFCUs?

MFCUs continue to work with state and federal agencies to stop fraud and abuse but also face increased federal scrutiny. On May 13, 2026, HHS Investigator General Bell sent a letter to every state Attorney General communicating a stance of “insistence on rigid MFCU compliance” with requirements and performance standards that will be enforced through “robust review” by the HHS-OIG. MFCUs are recertified annually on a rolling schedule, based on each specific state or territory’s original certification date.5 As of September 17, 2026, HHS-OIG has followed release of the May 2026 letter by issuing standard recertifications to 3 states and “conditionally recertifying” 11 state MFCUs, a designation which accompanies a set of corrective actions recommended by HHS-OIG. It does not appear that HHS-OIG regularly issued conditional recertifications prior to 2026.

In June 2026, Hawaii’s and New York’s MFCUs were notified that HHS-OIG was denying their annual recertification in letters citing insufficient case outcomes in both states. HHS announced that it was denying Hawaii’s and New York’s annual MFCU recertifications, discontinuing federal funding for the fraud control units. In each state’s recertification denial letter, HHS cites insufficient case outcomes (particularly low production of criminal indictments and convictions) and recoveries that are disproportionately low relative to the staffing and budget of the state MFCU (New York) or relative to the growth in the state’s Medicaid spending (Hawaii). States that have their MFCU recertification denied can appeal the decision and request that HHS-OIG reconsider; Hawaii indicated they intended to seek reconsideration. Hawaii and New York have responded to their denied MFCU certifications by reiterating their states’ commitment to Medicaid program integrity and highlighting ongoing actions to prevent and detect suspected Medicaid fraud. It is unclear if HHS-OIG may deny the recertification of other state MFCUs, but the discontinuation of federal funding could hamper states' ability to continue ongoing operations or initiate new investigations.

  1. MFCUs can also elect to investigate and prosecute patient abuse and neglect in non-institutional settings (e.g., home and community-based settings). ↩︎
  2. While states may have their own laws defining responsibilities around investigating beneficiary fraud or program abuse, MFCUs cannot use federal funding to investigate alleged beneficiary fraud unless it is in relation to suspected provider fraud. ↩︎
  3. Ibid. ↩︎
  4. Recoveries may not reflect the amounts actually collected from defendants (e.g., if the defendant is a company that dissolved before collections could be obtained). MFCUs work with state Medicaid agencies to return the state and federal share of any recovered Medicaid payments. ↩︎
  5. Federal requirements and performance standards serve as the basis for MFCU annual recertification by HHS-OIG. When a MFCU applies for annual recertification, the MFCU submits performance and budget data, including staffing, costs, case numbers and outcomes, and other information requested by HHS-OIG. HHS-OIG may conduct an onsite review of the MFCU. ↩︎

Proposed Changes to Demographic Data Collection in the Census Could Impact Efforts to Address Health and Health Care Disparities 

Published: Sep 25, 2026

Introduction

On September 10, 2026, the Census Bureau published a proposed rule adding two new parts to the regulations that govern the decennial census of population and housing. The proposed changes would prohibit the inclusion of questions on race and ethnicity (in addition to sexual orientation) and would narrow the definition of “usual residence” to exclude millions of noncitizen immigrants, including undocumented immigrants as well as lawfully present immigrants without lawful permanent resident status (i.e., LPR status or a green card) from the census’ apportionment count. This count is the official measurement used to proportionately divide the 435 seats in the U.S. House of Representatives across all 50 states. Further, under the proposed rule, the Census Bureau would consider tax records to determine “usual residence,” which could result in the exclusion of people who don’t file taxes from the census count. As outlined in the U.S. Constitution, the purpose of the decennial census is to count every person living in the U.S., with that information being used to determine “the number of seats each state has in the U.S. House of Representatives” as well as to distribute federal funds.

Since its inception in 1790, the census has always collected data on race and ethnicity and counted all persons living in the U.S., regardless of citizenship or immigration status. While President Trump attempted to exclude undocumented immigrants from the 2020 decennial census during his first term via executive action, legal challenges prevented the policy from being implemented. If finalized and implemented, the changes in the September 2026 proposed rule would mark the first time that race and ethnicity data are not collected in the decennial census and would also be the first time that millions of noncitizen immigrants, including those who are lawfully present but who lack LPR status, are excluded from U.S. population counts.

Public comments on the proposed rule are due by October 13, 2026, after which the Census Bureau is required to review and respond to comments before publishing a final rule. If finalized, the rule is likely to face legal challenges. A change in presidential administration prior to the 2030 decennial census could also impact implementation.

This issue brief provides an overview of the decennial census and discusses potential implications of the changes outlined in the proposed rule. Key takeaways include:

  • If finalized, the proposed changes to census data collection would signal the first time since its inception in 1790 that the U.S. decennial census does not collect data on race and/or ethnicity and excludes millions of noncitizen immigrants from apportionment counts.
  • The exclusion of millions of noncitizen immigrants from apportionment counts could lead to decreased federal funding and resources for states and localities with higher shares of immigrants. This includes funding for health programs such as Medicaid and the Children’s Health Insurance Program (CHIP).
  • Lack of race and ethnicity data could negatively impact research on health and health care disparities as well as data quality and representation since the decennial census is the only source of complete, block-level data on race and ethnicity as well as other key sociodemographic characteristics. Further, the exclusion of many noncitizens will also mean that the census will not accurately reflect who is residing in the U.S.
  • The proposed changes could impact the redistricting process and lead to shifts in political representation, including potentially reallocating congressional seats in ways that would reduce political representation for states with large immigrant populations.

The Decennial U.S. Census

The decennial census is constitutionally mandated to obtain a count of every person living in the U.S. to determine political representation and the allocation of federal funds. Beginning in 1790, the U.S. Census Bureau has conducted a census once every decade on April 1 in years ending in zero “to determine the number of people living in the United States.” The data collected by the decennial census are used to proportionately divide the 435 seats in the U.S. House of Representatives across all 50 states as well as to determine the allocation of hundreds of billions of dollars in federal funding annually.

The decennial census is the only source of complete, block-level (smallest geographic unit defined by the Census Bureau) data on race and ethnicity as well as other demographic characteristics. Researchers and organizations rely on census data to understand population distribution by key demographic characteristics, for drawing nationally representative survey samples and weighting surveys, and to do in-depth research in areas like the U.S. workforce, the economy, and housing stock, among others. The race and ethnicity data collected by the census are also used to evaluate the effectiveness of government programs and policies as well as to measure and ensure fairness, equity, and compliance with anti-discrimination laws and policies.

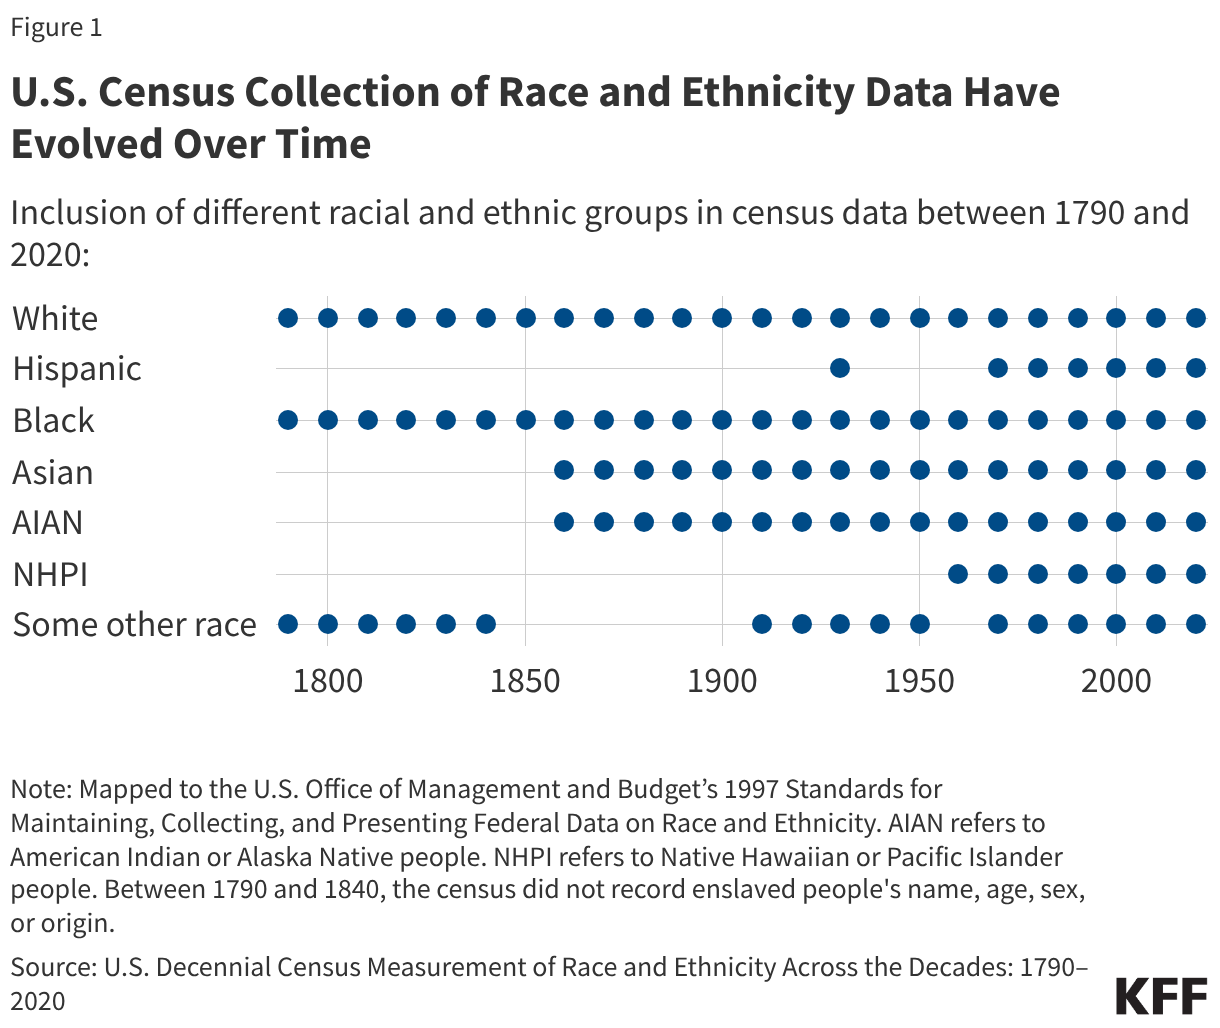
Since its inception in 1790, the U.S. census has collected information on race and ethnicity that has informed policy, the allocation of resources, and research on different groups within the country. How the census has collected and categorized information on race and ethnicity and the racial and ethnic groups for which data have been collected have evolved significantly over time, reflecting social and political shifts and the growing diversity of the U.S. population (Figure 1). In 1977, the Office of Management and Budget (OMB) established federal standards for collecting and reporting race and ethnicity data. The OMB standards guide not only the census but also other federal surveys, ensuring consistency across government data collection efforts. In March 2024, the OMB revised the racial and ethnic data collection and reporting standards to add Middle Eastern or North African as a category, clarify instructions for individuals to select multiple racial and ethnic categories, and require collection of more detailed data. The OMB indicated that these revisions were intended to result in more accurate and useful race and ethnicity data across the federal government. However, the Trump administration has extended the deadline for implementation of these changes twice and canceled plans to use the new standards in the 2027 American Community Survey.

U.S. Census Collection of Race and Ethnicity Data Have Evolved Over Time (Dot Plot)

Since its inception in 1790, the decennial census has included all people residing in the U.S. regardless of citizenship or immigration status, consistent with the Constitution's directive to enumerate "persons" rather than citizens. Article I, Section 2 of the U.S. Constitution requires an "actual Enumeration" of the population every ten years for purposes of proportionately dividing, or apportioning, seats in the U.S. House of Representatives, and Section 2 of the Fourteenth Amendment, which eliminated the Three-Fifths Compromise, specifies that representatives be apportioned "according to their respective numbers, counting the whole number of persons in each State…". Consistent with this description, the Census Bureau's longstanding practice has been to count every single “person,” regardless of citizenship or immigration status, who usually lives and sleeps in the U.S. in the decennial census. It has never excluded noncitizens from the apportionment base. During his first term, President Trump sought to exclude undocumented immigrants from the 2020 apportionment count through executive action, but legal challenges prevented the policy from taking effect.

Implications of Proposed Changes

The exclusion of millions of noncitizen immigrants from apportionment counts could lead to decreased federal funding and resources for states and localities with higher shares of immigrants. The proposed rule's exclusion of immigrants without LPR status from the U.S. resident population (in addition to the apportionment base) by redefining the term “usual residence” will impact the allocation of federal funds and resources across areas. The change will lead to areas with higher shares of noncitizen immigrants receiving less funding since the census will show them having fewer residents and the income and demographic profile of state residents may change without those noncitizens being counted. Prior research has found that, beyond total population counts, each state’s poverty rate and share of people living in rural areas are key factors that drive allocation of federal funds since they often are directed to low-income households and rural areas. According to analysis by the Project on Government Oversight, over 370 public programs relied on census data to allocate at least some portion of over $2.2 trillion in federal funds to states, counties, local communities, organizations, and households in fiscal year 2023. The largest share of this funding is for health programs, including Medicaid and CHIP. For example, the federal government’s share of most Medicaid and CHIP expenditures (or Federal Medical Assistance Percentage (FMAP)) is based on a state’s per capita income derived from decennial census data. Excluding many noncitizens--who are disproportionately likely to have lower incomes--from the resident count could result in a reduction in the FMAP for states with large immigrant populations, such as Florida and Texas. Other states that also have large immigrant populations, like California, would likely be affected less since their FMAP is already at the lowest level of 50%. The change could also affect the location of federally funded resources. For example, the Health Center Program uses census-derived data to determine medically underserved areas, which helps determine the location of Federally Qualified Health Centers (FQHCs). Decennial census data also indirectly shape where hospitals are located. For example, 36 states, including D.C., have certificate of need (CON) laws that help determine whether a new hospital or additional beds may be built using "bed need" methodologies that are benchmarked to census data.

Lack of race and ethnicity data and the exclusion of many noncitizen immigrants could negatively impact research on health and health care disparities as well as data quality and representation. Elimination of racial and ethnic data collection from the decennial census will have important implications for the measurement of disparities since the decennial census is the only source of complete, block-level data on race and ethnicity as well as other key sociodemographic characteristics. The exclusion of many noncitizens will also mean that the census will not accurately reflect who is residing in the U.S. Changes to the data beginning with the 2030 decennial census will eliminate a key source of data researchers use to understand population demographics and to ensure surveys are nationally representative and also limit the ability to examine trends over time, since the data will not be comparable to earlier versions. In the proposed rule, the Census Bureau indicates that they are not proposing restrictions on asking demographic questions on the American Community Survey or other surveys that are not used for enumeration of the population. While the administration is not currently proposing changes to such surveys, if similar changes are made to these surveys in the future, that would further limit the ability to understand the demographics of the U.S. population and the ability to measure and address health and health care disparities.

The proposed changes to stop collecting data on race and ethnicity are also likely to affect the redistricting process and lead to shifts in political representation. Decennial race and ethnicity data obtained from the census underpin the redistricting process and consequently, the voting power of communities of color. Under public law 94-171, enacted in 1975, the Census Bureau is required to provide states with block-level demographic data from the decennial census to redraw congressional and state legislative districts based on updated population counts. Section 2 of the Voting Rights Act (VRA) of 1965 prohibits voting practices that discriminate on the basis of race, among other factors. Block-level data on race and ethnicity cross-tabulated by voting age have long been used to establish the threshold required to bring a vote dilution claim under the law. In April 2026, the Supreme Court's decision in Louisiana v. Callais narrowed Section 2, holding that plaintiffs must show a strong inference that a state intentionally drew districts to afford minority voters less opportunity because of race as well as offer alternative maps meeting the state's legitimate goals. Eliminating block-level racial and ethnic data would compound these heightened evidentiary requirements by removing the underlying data to identify vote dilution, draw districts that provide communities of color an opportunity to elect candidates of their choice, and litigate VRA claims in the future.

The exclusion of millions of noncitizen immigrants from the decennial census could lead to the reallocation of congressional seats in ways that would reduce political representation for states with large immigrant populations. According to Pew Research Center, as of 2023, there were roughly 14 million undocumented immigrants and over 2 million lawfully present immigrants without LPR status in the U.S. Although these numbers have likely fallen since 2023, omitting these people from the count could impact representation for states with large numbers of immigrants. For example, a Pew Research Center analysis of President Trump’s earlier proposal to exclude undocumented immigrants from the 2020 decennial census found that, at that time, California, Florida, and Texas would each lose one congressional seat due to the change in population counts, while three other states would gain seats (Alabama, Minnesota, and Ohio).