Individual Market Enrollment Continues to Fall Through Mid-2026

Published: Oct 14, 2026

Enrollment in the individual health insurance market fell 18% between June 2025 and June 2026. The individual market is composed primarily of people with Affordable Care Act (ACA) Marketplace coverage as well as some people who buy similar coverage off-exchange. This represents an even steeper drop in enrollment than had previously been reported. Previous data on ACA Marketplace enrollment showed that effectuated enrollment fell 12% from February. Although more current data for the ACA Marketplace population are not yet available, data on the individual market—of which roughly nine in ten people are enrolled through the ACA Marketplaces—suggest enrollment continued to decline, falling 16% as of March and 18% as of June. This decrease includes both on- and off-exchange coverage. In total, we estimate that individual market enrollment has fallen by over 4.6 million people, from 25.2 million in June 2025 to 20.5 million in June 2026.

The enrollment decline coincides with the expiration of the enhanced premium tax credits and other policy changes that are expected to reduce enrollment. As of earlier this year, ACA Marketplace enrollment had fallen in every state except New Mexico, with wide variation in the size of the declines.

Individual Market Enrollment Declined by 18% Since June 2025 (Column Chart)

The decline in the individual market enrollment began during the 2026 ACA Marketplace Open Enrollment Period and continued throughout the year. Plan selections, or sign-ups, during the 2026 Open Enrollment Period fell by 1.2 million people from 2025. But plan selections may include people who do not pay their premiums and so never have coverage take effect. Returning subsidized enrollees also have a three-month grace period for nonpayment: those who do not make their premium payments are not dropped from coverage until the grace period elapses. Enrollees that did not make their January premium payment likely were not recorded as terminated until after March 31, with coverage terminated retroactively to the end of January. As a result, February ACA Marketplace effectuated enrollment (measured retrospectively after the grace period elapsed on May 15, 2026) fell by 12%, from 21.8 million to 19.2 million.

Year-over-year March enrollment in the composite individual market showed a continued decrease, falling 16%. By June, enrollment had fallen 18% compared with the same period in 2025. While these numbers include off-exchange enrollment, the bulk of individual market coverage is purchased on-exchange through ACA Marketplaces. Off-exchange coverage, purchased directly from insurers or brokers, does not provide access to financial assistance through premium tax credits but allows insurers additional flexibility in plan design.

These declines approach the Congressional Budget Office (CBO)'s projection of a roughly 25% drop in enrollment through 2026 after the expiration of the enhanced tax credits, and they are consistent with KFF polling of Marketplace enrollees. In KFF’s Follow-Up Survey of ACA Marketplace Enrollees, one in six returning enrollees (17%) said they were not confident they could afford their premiums for all of 2026, which puts them at risk of losing coverage later in the year. Among all 2025 Marketplace enrollees, 22% said they had moved to another source of coverage, and nearly one in ten (9%) said they were now uninsured.

Further enrollment declines may continue this and in upcoming plan years. The second-quarter data provide a mid-year snapshot, and enrollees who fall behind on premiums later in the year may still lose coverage. These June enrollment figures do not account for the drop in enrollment expected from the recent announcement of plan cancelations, which occurred after the end of the second quarter. While enrollment has fallen sharply this year, individual market enrollment is still higher than before the introduction of enhanced premium tax credits by over seven million from June 2019, a change of 53%.

Premiums are also expected to keep rising in 2027. Marketplace insurers have proposed a median premium increase of 15% for 2027, the second consecutive year of double-digit increases. On average, insurers raised premiums by an additional four percentage points in anticipation of further expected enrollment declines and a subsequently sicker risk pool in 2027. As some enrollees encounter higher premiums during the upcoming ACA Open Enrollment Period this fall, enrollment in the individual market may continue to shrink, and more people could become uninsured.

Methods

Data used in this analysis come from the Mark Farrah Associates Health Coverage Portal™. Data from the “Enrollment by Segment” exhibit and the “Accident & Health Policy Experience Exhibit – by Domicile” were used (accessed September 23, 2026). The dataset analyzed in this report includes plans filing the Exhibit of Premiums, Enrollment and Utilization (EPEU)—or the Supplemental Health Care Exhibit (SHCE) when EPEU is not available—with the National Association of Insurance Commissioners (NAIC) and California HMOs regulated by California’s Department of Managed Health Care. Only plans that were categorized as having a “medical” focus were included; “specialty” plans, which is composed of ancillary or supplemental benefit plans, were excluded. Enrollment from the U.S. territories was excluded. Enrollment counts were adjusted to exclude Children’s Health Insurance Program (CHIP) enrollment that may be captured as individual market enrollment for all plans with available data in the Policy Experience exhibit. Enrollment in plans that file SHCE annually at the end of the year (such as life plans that may sell health insurance in the individual market) was also adjusted by the national growth rate from the end of the preceding year to estimate second quarter enrollment. The share of total individual market enrollment derived from SHCE was 2.8% in 2025 and 1.5% in 2026. Among insurers that report quarterly, there was a 5% drop in enrollment between March and June 2026.

Mark Farrah Associates released a report that estimated enrollment fell about 17.2% year-over-year in the second quarter of 2026. The KFF analysis differs by including only plans with a medical focus in the U.S. excluding territories, adjusting for plans that file annually and for CHIP enrollment.

HHS Public Health Policy Actions Under the Trump Administration 2025-2026

Published: Oct 13, 2026

Note: Originally published on Nov. 12, 2025, this resource is updated as needed, most recently on October 12, 2026, to reflect additional developments. 

Since assuming office for a second term, President Trump and officials in his administration have instituted numerous policy actions through the Department of Health and Human Services (HHS) affecting public health in the U.S. This resource lists and briefly describes key actions in the order in which they were first issued, reported or announced, with subsequent linked actions and related outcomes also included with each entry. As new policy changes occur, they will be added. 

This resource is not meant to be exhaustive of all administration actions related to public health, as many other federal policy changes – including outside of HHS – have public health implications but are not captured here.

Additional KFF resources on administrative actions related to global health, LGBTQ+ health, and mental health and substance abuse are also available.

Date

|

Action/Description

January 20, 2025Presidential Executive Orders precipitate removal of some HHS websites and health data.
– In the first days of his second term President Trump issued a number of Executive Orders (EOs), including EOs that revoked many Biden administration orders and programs, and instituted new federal guidance related to “gender ideology,” “diversity, equity, and inclusion (DEI),” and “merit-based opportunities.” These EOs have implications for public health, particularly related to the collection and presentation of data and websites by the federal government. For example, in response to the EOs, HHS began to remove thousands of websites and numerous federal databases with public health information deemed to be related to DEI, LGBTQ, reproductive health, HIV/AIDS research, health disparities, and more, and limited some data collection and analysis in these areas. A lawsuit was filed to reverse these removals, and some information has been restored over time. In September, the administration agreed to restore all previously removed health-focused websites and data to versions that had existed on January 29, 2025.
February 7, 2025NIH announces change to indirect cost rate guidance.
– As part of grants for health research, the National Institutes of Health (NIH) provides “indirect cost” funding to grant recipients, which supports administration and facilities costs at grantee institutions. On February 7, NIH announced it would apply a new 15% “standard indirect cost rate” on all grants, which would apply to any new grants and to existing grants for expenses as of February 10, 2025. This was challenged in federal court and federal judges placed holds on the policy, first through a temporary restraining order affecting 22 states on February 10, a nationwide preliminary injunction on March 5, and a permanent injunction on April 4; prior rates still apply for the time being. The administration appealed the ruling and legal proceedings continue. If implemented, a 15% indirect cost rate would be a much lower rate compared to historical NIH rates and would amount to a significant cut in funding for institutions performing NIH-sponsored health research.
February 13, 2025Robert F. Kennedy, Jr. confirmed as HHS Secretary under President Trump.
– The Senate voted 52-48, along party lines, to confirm Robert F. Kennedy, Jr. as the Secretary of Health and Human Services.
February 13, 2025President Trump issues Executive Order (EO) establishing MAHA policy agenda and MAHA Commission.
– The EO outlines the purpose and objectives of the Trump administration’s Make American Healthy Again (MAHA) efforts. Stating that the U.S. must “re-direct our national focus…toward understanding and drastically lowering chronic disease rates and ending childhood chronic disease,” it directs federal agencies to “aggressively combat” mental health disorders, obesity, diabetes, and other conditions. It also establishes the MAHA Commission to advise the President, naming Secretary Kennedy as Chair. The EO directs the Commission to submit an assessment on how to combat the “childhood chronic disease crisis” within 100 days, and a strategy to address the crisis within 180 days, setting in motion processes to develop further public health strategies and plans (discussed in other entries below). 
February 14, 2025White House, DOGE initiate “reduction in force (RIF)”, including for HHS personnel.
– The EO outlines the purpose and objectives of the Trump administration’s Make American Healthy Again (MAHA) efforts. Stating that the U.S. must “re-direct our national focus…toward understanding and drastically lowering chronic disease rates and ending childhood chronic disease,” it directs federal agencies to “aggressively combat” mental health disorders, obesity, diabetes, and other conditions. It also establishes the MAHA Commission to advise the President, naming Secretary Kennedy as Chair. The EO directs the Commission to submit an assessment on how to combat the “childhood chronic disease crisis” within 100 days, and a strategy to address the crisis within 180 days, setting in motion processes to develop further public health strategies and plans (discussed in other entries below). 
February 14, 2025President Trump issues Executive Order prohibiting federal funding to schools and universities with COVID-19 vaccine requirements.
– The EO requires HHS to work with the Department of Education to prohibit COVID-19 mandates in schools, by issuing guidelines for compliance and barring federal funds from going to any educational agency, K-12 school, or institution of higher education that requires COVID-19 vaccination to attend in-person education programs (educational vaccine mandates are set at the state level). Educational vaccine requirements are set at the state and local levels. At the time the EO was released in February, no state required K-12 students to be vaccinated against COVID-19 while 15 colleges required Covid vaccines for students. However, by March 14, 2025 all of those colleges had ended their COVID-19 vaccine requirements for students.
February 18, 2025Secretary Kennedy announces public health policy priorities during HHS welcome ceremony.
– In his first remarks to HHS staff, Secretary Kennedy announces the public health priorities for his tenure. This include investigating the childhood vaccine schedule, tackling corruption and promoting transparency, and addressing a “chronic disease epidemic” especially in children, which he says may be linked to pesticides, food additives, antidepressants, microplastics, cellphone emissions, and other factors.
February 28, 2025Secretary Kennedy issues new rule ending public comment requirement for HHS grants and contracts.
– The new rule rescinds a prior HHS policy on “Public Participation in Rule Making” (the “Richardson Waiver,” dating back to 1971) and “re-aligns the Department’s rule-making procedures with the Administrative Procedure Act.”  As a result, “matters relating to agency management or personnel or to public property, loans, grants, benefits, or contracts” are exempt from the notice and comment procedures. This removes what had been a key step in the rulemaking process requiring public notification and a comment period. For example, changes to HHS policies related to work requirements for Medicaid and NIH funding would no longer require public comments under the new rule. This could streamline implementation of HHS policy, but also reduce public visibility on changes before they take effect.  Some lawmakers and public health focused groups have asked HHS to return to the prior requirements under the Richardson Waiver. 
March 7, 2025HHS announces that CDC will conduct a study of factors contributing to the rise in autism in the U.S.
– In statements to the press, HHS officials indicate CDC will initiate a study looking at the factors that are contributing to the rise in autism diagnoses in the U.S.. To date, no new CDC study results on this topic have been released though in a related development, in September 2025 President Trump and HHS leadership announced at a press conference and through a White House Fact Sheet that they believe there is a link between acetaminophen (e.g., Tylenol) use in pregnancy to autism (further details provided below). President Trump and Secretary Kennedy both have a history of linking vaccines and autism, even though there is no evidence of such a link.
March 13, 2025Food and Drug Administration (FDA) releases guidance on 2025-2026 influenza vaccine composition.
– The FDA guidance identifies which influenza virus strains manufacturers should use as components of 2025-2026 influenza vaccines. To develop these recommendations, FDA convened meetings of federal scientific and public health experts, including from FDA, CDC, and Department of Defense, but did not consult with the FDA’s Vaccines and Related Biological Products Advisory Committee (VRBPAC) or other professional groups outside the government. FDA had canceled the scheduled VRBPAC meeting on this topic, and the lack of input from outside experts was a break from past years’ practices. In addition, in past years there was active participation and coordination between U.S. federal experts and global technical experts working under the auspices of the World Health Organization (WHO), but official communications with WHO-linked experts has been curtailed since the Trump administration announced in January 2025 that the U.S. was withdrawing its membership from the UN agency.
March 17, 2025NIH initiates termination of numerous grants for HIV prevention and treatment programs.
– The canceled NIH grants include support for researchers investigating use of PrEP, medication used pre-exposure to prevent HIV infections, and programs focused on HIV/AIDS in adolescents and young adults. Even as the first Trump administration supported HIV/AIDS prevention and treatment efforts, including through a highly visible federal effort to “end the HIV epidemic” in the U.S. by 2030, these same programs have now been targeted for cuts (further details below).   
March 17, 2025HHS removes Surgeon General warning declaring gun violence a public health crisis.
– The HHS website was changed, removing a 2024 advisory from the Surgeon General on the public health impacts of gun violence. In addition to removing the Surgeon General’s warning, the administration has rolled back a number of gun safety policies in place during the Biden administration. The White House Office of Gun Violence Prevention, established during the Biden administration was shut down in early 2025. Further, significant numbers of staff at CDC’s Injury Center, which collects data on violent deaths and injuries, and CDC’s Division of Violence Prevention have been let go as part of the Trump administration’s reduction in force efforts.
March 25, 2025HHS and CDC seek to pull back $11 billion in supplemental COVID-19 and public health funding from state and local health departments.
– In a statement, HHS says it intends to pull back $11.4 billion in supplemental funding that had been provided by Congress for state and local public health departments through CDC for pandemic response activities. Following the announcement, on April 1, a group of 23 mostly Democratic-led states sued the Trump administration over the attempt to pull back this funding.  On April 3, a federal judge placed a temporary block on the administration’s actions, and on May 16, another federal judge indefinitely blocked the administration from enacting its funding pull back for the states that are part of the lawsuit. As of late August 2025, almost 80% of the funds initially targeted for cuts by the Trump administration had been restored for the 23 states that won in court. However, funding has not been restored to the remaining states, the majority of which are Republican-led.
March 27, 2025HHS announces a major re-organization and job cuts plan.
– HHS announces plans for a major restructuring of the department, in accordance with President Trump’s February 26 EO on “Implementing the President’s ‘Department of Government Efficiency’ Workforce Optimization Initiative.” The announcement says HHS will create an Administration for a Healthy America (AHA), which would combine several existing HHS offices including the Office of the Assistant Secretary of Health (OASH, which contains the Surgeon General’s Office), the Health Research and Services Administration (HRSA), the Substance Abuse and Mental Health Services Administration (SAMSHA), the Agency for Toxic Substance and Disease Registry (ATSDR), and the National Institute for Occupational Safety and Health (NIOSH). In addition, the Administration for Strategic Preparedness and Response (ASPR) at HHS would be moved under CDC. The announcement also says HHS will reduce its workforce by eliminating 10,000 full-time positions. Combined with other reduction in force efforts, a total of 20,000 HHS workers are expected to lose their jobs.

On May 5, a coalition of 19 Democratic-led states and the District of Columbia filed a lawsuit against the mass firing of federal health workers and re-organization of HHS. On May 10, a court ordered a temporary pause on sweeping federal firings at HHS and other agencies. On July 1, a federal judge blocked mass firings at HHS, saying they are likely unlawful. However, on July 8 the Supreme Court overturned the lower court decisions, allowing the Trump administration to proceed with job cuts. As of August it is estimated that over 20,000 jobs at HHS have already been cut, meaning the administration already met its initial workforce reduction goal.

Regarding re-organization, some organizational changes have been implemented at HHS, with major cuts or closures to public health related offices such as the HHS Office of Infectious Diseases & HIV Policy, the HHS Office of Minority Health, and HRSA’s Bureau of Primary Health Care.  However, other proposals such as the formation of an Administration for a Healthy America (AHA), have not yet been implemented. Implementing AHA to the extent proposed is likely to require approval from Congress, though so far Congress has not acted on legislation codifying these proposals.
March 31, 2025HHS withholds portion of Title X family planning service grants. 
– HHS notifies one in five current grantees of the federal Title X family planning program that a portion of their funding would be temporarily withheld. This funding freeze affects all nine Planned Parenthood grantees, in addition to 7 other nonprofit grantees, and it is estimated that a total of 879 clinics (24% of all Title X clinics) in 23 states are affected. After several months, funds were reinstated to some organizations, but the Planned Parenthood grantees have still not had their funding reinstated.
April 1, 2025HHS ends federal support for the “Safe to Sleep” program, which focuses on prevention of infant deaths during sleep.
– The Trump Administration ends federal participation in Safe to Sleep, a national campaign that focused on educating parents of newborns about safer sleeping practices for infants that can prevent death. The program, supported through the NIH’s National Institute of Child Health and Human Development (NICHD) Office of Communications in recent years, had been in existence for over 30 years and had contributed to a major decline in sudden infant deaths. The NICHD office was eliminated on April 1, along with federal support for “Safe to Sleep.”
April 2, 2025HHS requires CDC to reduce contract spending by $2.9 billion as part of DOGE cost reduction efforts.
– According to reports, HHS orders CDC to reduce its contract spending by $2.9 billion by April 18.CDC contract funding has been used to support several services at the agency including security, cleaning, and computers/technology. The sudden requirement to cut this spending by approximately 35% affects CDC operations. 
April 7, 2025HHS Secretary Kennedy announces changes to fluoride policies.
– Secretary Kennedy announces a plan to implement a number of changes to federal policy related to water fluoridation, including stating that CDC will stop recommending water fluoridation as a public health intervention (though to date, HHS and CDC still recommend community water fluoridation). In addition, Kennedy says the defunct Community Preventive Services Task will be revived and reconvened, with a goal of studying and making recommendations about water fluoridation. Kennedy also called on states to ban fluoride in their drinking water. Already this year Utah and Florida have banned community water fluoridation, the first states ever to do so.
April 17, 2025FDA informs Pfizer/Moderna that mRNA COVID vaccines will require an expanded warning label about myocarditis.
– In letters sent April 17, the FDA informs Pfizer and Moderna they must alter the warning labels for their COVID-19 mRNA vaccines to include expanded risks for myocarditis and pericarditis. Previously, the warning labels for these vaccines noted risks for these conditions for those aged 18 to 24 years (Moderna) and 12 to 17 years (Pfizer). However, updated labels are required to include new language saying “the observed risk of myocarditis and pericarditis following vaccination with mRNA COVID-19 vaccines has been highest in males 12 through 24 years of age” and that “persistence of abnormal cardiac magnetic resonance imaging (CMR) findings that are a marker for myocardial injury was common.”  According to FDA, the labels must also include more information about these conditions and their health risks.  Since the letters were sent, the companies have complied with the new FDA requirements. FDA approved the updated label language on June 25.
April 22, 2025FDA and HHS announce measures to phase out use of petroleum-based food dyes.
– FDA and HHS announce a series of steps the federal government will take to remove petroleum-based synthetic dyes from the U.S. food supply. These actions include initiating a process to revoke federal authorization for two such dyes and planning phase-outs by the food industry for others. In addition, the government will support research on food additives and children’s health and authorize natural alternative coloring options. Under the current plan, the phase-outs will occur through voluntary action taken by food companies.
May 1, 2025HHS announces a $500 million investment in a “next generation universal vaccine platform.”
– HHS and NIH announce that $500 million in funding will be directed to a new effort  to develop a “universal vaccine platform for pandemic-prone viruses.” The platform uses inactivated whole viruses, and is part of a broader federal effort to develop universal vaccines called “Generation Gold Standard.” The funds for this new investment appear to be re-purposed vaccine development funds from the Biden Administration’s NextGen initiative to develop next generation COVID-19 vaccines.
May 2, 2025White House Releases FY 2026 President’s Budget Request calling for major fundings cuts at HHS.
– The White House released an outline of the administration’s budget request for FY2026 and on May 30, the White House submitted the full Budget Request for FY2026 to Congress. The request proposes steep cuts to the HHS budget, including cuts for CDC, HRSA, SAMHSA, NIH, eliminating the Hospital Preparedness Program at ASPR, and reducing funding and cutting some programs focused on HIV/AIDS research and response. The budget request also asks Congress for $500 million to support a new “Administration for a Healthy America (AHA)” and MAHA-related priorities. The President’s Budget Request is only a proposal, as it is Congress that ultimately decides how much money the federal government appropriates. So far, Congressional spending bills for FY2026 have not included cuts to HHS of the magnitude requested by the President, and Congress has not provided the requested $500 million for AHA though budget negotiations continue.   
May 5, 2025White House Executive Order restricts funding and increases oversight for “gain of function” research at HHS.
– In an EO titled “Improving the Safety and Security of Biological Research” the White House cites concerns with federally funded “gain-of-function” (GOF) research on biological agents and states the Biden administration allowed dangerous GOF research to occur without sufficient oversight. The EO directs the Secretary of HHS to coordinate with other relevant Executive branch offices to establish guidance to end federal funding of “foreign entities” where GOF is being undertaken or in countries lacking oversight of GOF research. The EO requires the relevant Executive offices to submit updated policies and guidance for all federally supported GOF-related research, and to develop a strategy for managing risks of non- federally funded GOF research. The full implications of the EO are not yet clear, as the Executive branch offices must develop and implement specific guidance and regulations. According to outside experts, potential benefits of the EO include more transparency and stricter enforcement of dangerous research, while potential risks include hindering beneficial research that is not GOF and researchers choosing to curtail beneficial research to avoid potential repercussions under evolving federal restrictions.
May 20, 2025FDA leaders announce clinical trials will be needed for approval of certain new COVID vaccine formulations.
– In a medical journal article, FDA leaders indicate that going forward, for federal approval of new or updated COVID-19 vaccines (“boosters”) for use in individuals who are not considered at higher risk (defined as persons 65 or older or those with certain health conditions), will require vaccine makers to present evidence from randomized, placebo-controlled trials that demonstrate safety and efficacy. The announced policy is a departure from prior years when FDA did not require new trial data to authorize or approve boosters, but instead allowed approvals based on immune response evidence. The new policy could hinder investments by pharmaceutical companies in developing new COVID vaccine formulations, given the greater expense and time required to conduct new, full clinical trials.
May 22, 2025MAHA Commission Report on childhood chronic disease published.
– The first official report from the MAHA Commission (established by the February 13 EO discussed above) discusses factors contributing to a “chronic disease crisis” for U.S. children and provides a “call to action”. The report highlights four main drivers of the crisis: poor diet (primarily due to consumption of ultra-processed foods), exposure to chemicals, lack of physical activity and chronic stress, and “overmedicalization (excessive use of prescription drugs, such as antidepressants). The report calls for federal agencies to “close critical research gaps and guide efforts to better combat” these issues. It also says the MAHA Commission will develop and release a strategy in August (discussed below). The report expanded on the ideas initially outlined in the February EO and provided more details on Secretary Kennedy’s priorities to address chronic disease in children. There was some criticism of the report after its publication, with experts questioning some of the evidence and conclusions and pointing out significant errors and studies cited that did not exist, which indicated that artificial intelligence was likely used to help write the report. 
May 23, 2025Administration ends NIH funding for several HIV vaccine research projects. 
– NIH notifies two grant recipients working on broadly neutralizing antibody research for HIV vaccines of the cancelation of their funding.  The canceled grants supported early-stage vaccine development research that uses a different approach than other HIV vaccine candidates. Some other HIV vaccine candidates remain in the development pipeline and clinical trials continue, but the absence of this early-stage research could jeopardize the development of additional candidates going forward.
May 27, 2025HHS Secretary Kennedy announces CDC will no longer recommend COVID vaccines for healthy pregnant women and children.
– In a video post on X, Secretary Kennedy announces “the COVID vaccine for healthy children and healthy pregnant women has been removed from the CDC recommended immunization schedule.” The announcement was a departure from the typical process for changing vaccine recommendations, which includes review and input from the Advisory Committee on Immunization Practices (ACIP) and a notification from the CDC Director. Initially, the implications of changing CDC guidance without ACIP input were unclear given that no-cost insurance coverage for vaccination is linked to ACIP and CDC recommendations. On May 30, CDC changed the language on its website for COVID-19 vaccines, removing its prior recommendation for pregnant women to be routinely vaccinated and stating that healthy children 6 months to 17 years old could be vaccinated in consultation with health care providers/parents – a recommendation known as “shared decision-making,” which would mean insurance would still have to cover such vaccinations. On July 7, a coalition of professional medical organizations filed a lawsuit against HHS over the new COVID-19 vaccine recommendations, saying the department did not follow federal procedures in making the change and also mislead the public on the issue (on January 6, 2026, a federal court confirmed these plaintiffs have standing to challenge HHS’s actions on the COVID-19 vaccine recommendations, allowing the case to proceed to arguments). On August 19, independent expert groups, including the AAP, issued their own recommendations for COVID vaccines in infants and young children in contrast with CDC’s new recommendations.  On Aug 22, ACOG issued their own recommendations for pregnant patients.
June 9, 2025HHS Secretary Kennedy announces removal of all sitting members of ACIP.  
– In a post on X and a subsequent HHS press notice, Secretary Kennedy announces that all 17 sitting members of the CDC’s Advisory Committee on Immunization Practices (ACIP) are dismissed, to be replaced with new members selected by the Secretary. Kennedy says the move is “prioritizing the restoration of public trust above any specific pro- or anti-vaccine agenda.” The HHS Secretary does have the discretion to remove and nominate ACIP members, though no previous Secretary has dismissed all ACIP members at once. In a subsequent X post on June 11, Kennedy announces the nomination of eight new members to ACIP, several of whom have been critical of COVID-19 vaccines and have expressed concerns about harms caused by vaccinations more generally. In a later press release from September 15, HHS announces five more members to be appointed to ACIP, including several with a history of criticism of COVID-19 vaccine policies. 
June 17, 2025FDA announces National Priority Vouchers for expedited regulatory review of new drugs that support “U.S. national interest.”
– FDA announces a Commissioner’s National Priority Voucher (CNPV) program, which can be “redeemed by drug developers to participate in a novel priority program” that shortens regulatory review time from 10-12 months to 1-2 months. FDA says it will determine the availability of vouchers for companies that are aligned with the “national health priorities” of: addressing a health crisis in the U.S.; delivering more innovative cures for the American people; addressing unmet public health needs; and, increasing domestic drug manufacturing as a national security issue. On October 16, FDA announced the first nine CNPV recipients, and on November 6, announced six more recipients.  The impact of this new priority voucher program on speeding drug approvals and onshoring drug manufacturing capacity is as yet unclear. In addition, there are several other existing priority review processes at FDA so adding another could strain FDA staff capacity at the same time there has been significant reductions in FDA’s staff and budget.  These strains have already slowed FDA review times in general.
June 18, 2025FDA approves lenacapavir – a new HIV prevention drug.
– FDA approves Gilead Sciences’ lenacapavir, a new injectable PrEP drug that has been shown to be highly effective at preventing HIV infection, and which requires just one dose every 6 months, making it the first ever twice-a-year drug option for HIV prevention. In September, CDC issued clinical guidance for use of injectable lenacapavir as PrEP, though that guidance did not include reference to transgender people, a group intentionally included in the clinical trials and at increased risk of HIV. FDA’s approval also precipitated a review by the World Health Organization (WHO) and on October 6, WHO pre-qualified lenacapavir for prevention of HIV. WHO pre-qualification can speed regulatory approval for the drug in many low- and middle-income countries with a high burden of HIV/AIDS and can also allow for global health mechanisms like the Global Fund to Fight AIDS, Tuberculosis and Malaria to procure the drug.
June 25-26, 2025The newly reconstituted ACIP makes recommendations and policy changes related to RSV and influenza vaccines, and designates new workgroups on hepatitis B, MMRV, and the childhood immunization schedule.
– ACIP votes to recommend respiratory syncytial virus (RSV) injections for babies and RSV vaccine for people 50 and older, and a ban on the use of thimerosal in multi-dose influenza vaccine vials. ACIP also agrees to stand up three new workgroups that will review the U.S. childhood vaccination schedule, hepatitis B guidance, and combination MMRV vaccine.  Subsequently, on July 3, CDC issued new RSV guidance that mirrored ACIP recommendations. On July 23, Secretary Kennedy enacted ACIP’s recommendation on thimerosal, rescinding federal recommendations for any influenza vaccines containing thimerosal (a change that only affects a very small percentage of the overall influenza vaccine market that is comprised of multidose vials).
July 1, 2025HHS alters program requirements and withholds funding from sex education and teen pregnancy prevention programs.
– HHS notifies all Teen Pregnancy Prevention (TPP) program grantees and Personal Responsibility Education Program (PREP) grantees in 46 states and territories that their material must align with President Trump’s executive orders, including those that ban the promotion of gender inclusivity, risk losing federal funding. TPP is a national grant program that funds grantees to replicate, develop, test, and evaluate evidence-based approaches to prevent teen pregnancy, while PREP awards grants to state agencies to use evidence-based models in educating adolescents on both abstinence and contraception. In August, the Trump administration cancelled a $12.3 million PREP grant to California after state officials refused to revise curricula in compliance with the EOs. In September 2025, 16 states and D.C. sued HHS alleging that the new PREP grant conditions are unlawful, unconstitutional, and harmful to gender diverse youth. Similarly, a federal judge blocked the HHS policy changes for TPP in October 2025.
July 2, 2025CDC deactivates its emergency response for H5N1 influenza (bird flu) and limits tracking and reporting of data on bird flu infections in humans and animals.
– CDC ends its emergency response for H5N1 bird flu in the U.S., which had been active since April 4, 2024. CDC reports the change is due to a decline in animal infections and no reports of human cases since February 2025. CDC also says data on the number of people tested for H5N1 will be reported only monthly, and no further data on infection rates in animals will be reported on the CDC website. Even so, reporting from states showed the number of H5N1 cases in birds, which had declined over the summer, began to increase again in fall 2025. However, much of the federal research and response efforts for H5N1 have been closed down or significantly limited following funding and staff cuts and a prolonged government shutdown. The limited federal tracking and reporting of H5N1 infections can slow identification of outbreaks and potentially slow response times.
July 9, 2025HHS Secretary Kennedy cancels a scheduled meeting of the U.S. Preventive Services Task Force (USPSTF).
– Secretary Kennedy cancels a meeting of the USPSTF several days before it was scheduled to take place, with no reason given and no re-scheduled meeting date provided. Typically, the task force meets three times a year, though no meeting has yet occurred under Secretary Kennedy. USPSTF is responsible for reviewing and recommending preventive health services. USPSTF recommendations have implications for what services insurers must cover with no cost-sharing, under the Affordable Care Act (ACA). Such services can include screening tests, behavioral counseling, and medications that can prevent diseases and illness (other than vaccines, which are tied to ACIP recommendations). However, along with other parts of the ACA, USPSTF has faced court challenges. On June 27 (prior to Kennedy’s cancelation of the meeting), while the Supreme Court ruled the ACA requirement that insurers cover USPSTF-recommended services is indeed constitutional, it also found that the HHS Secretary has the power to add and remove USPSTF members at will, which underscores the possibility that Secretary Kennedy may choose to dismiss some or all of the existing USPSTF members and appoint new members (as Kennedy has done with ACIP), or simply not name any new members, and has the power to choose not to adopt USPSTF recommendations. In light of Kennedy’s cancellation and the Supreme Court ruling, 104 public health focused organizations called on Congress to “protect the integrity of the USPSTF” through legislative action. The subsequent USPSTF meeting was scheduled to occur in November but that was also canceled, with HHS citing the government shutdown as the reason. Meetings in March 2026 and July 2026 were also canceled.
July 31, 2025FDA announces new safety label requirement for opioid pain medications.
– The FDA says will require safety labels on opioid medications so that users can better understand that risks of long-term opioid use. The updated labels should include a summary on the risk of addiction, misuse, and overdose, treatment guidance and the risk of higher doses, how to safely discontinue opioid use, drug interactions, digestive complications, and overdose reversal medications. Drug companies received notification letters and have 30 days to submit updated labels for review.
July 31, 2025HHS Secretary Kennedy swears in Susan Monarez as CDC Director.
– In a statement welcoming the newly Senate-confirmed CDC Director, Secretary Kennedy says Monarez has “unimpeachable scientific credentials” and he has “full confidence in her ability to restore the CDC’s role as the most trusted authority in public health.” However, 28 days later (on August 27) the White House removed Monarez from her position at CDC. According to Kennedy, she was removed because he lost trust in her ability to serve as CDC Director and to implement the policies of the Trump Administration. According to Monarez, she was removed because she would not provide “blanket approval” for vaccine policy changes in advance and would not fire, as requested by Kennedy, CDC employees without cause. On August 28, Secretary Kennedy announced in a letter to CDC staff that Deputy Health and Human Services Secretary Jim O’Neill would serve as acting CDC Director.
August 1, 2025Newly announced CDC policy prevents outside professional medical and public health organizations from participating in working group meetings of ACIP.
– Officials at HHS notify professional medical organizations such as the American Academy of Pediatrics (AAP), the American Medical Association (AMA), the American College of Obstetricians and Gynecologists (ACOG), and others that they will be excluded from joining ACIP working group discussions going forward. Professional groups representing medical doctors and other stakeholders in vaccine policies have long participated as non-voting members, including in ACIP working groups. Working groups are typically responsible for helping review available data about topics prior to ACIP meetings, and helping develop recommendation language for ACIP to vote on, as well as other activities in support of ACIP. While the outside groups can be present and can participate in full ACIP meetings, the new policy removes them from providing any input through working groups.
August 5, 2025HHS announces a “coordinated wind down” of $500 million in federal funding for mRNA vaccine research. 
– HHS announces that it will cancel and begin to wind down mRNA vaccine development activities funded through the Biomedical Advanced Research and Development Authority (BARDA). In total, HHS reports it is canceling 22 projects worth nearly $500 million because “these vaccines fail to protect effectively against upper respiratory infections like COVID and flu…Going forward, BARDA will focus on platforms with stronger safety records and transparent clinical and manufacturing data practices.”  mRNA COVID-19 vaccines are effective in preventing severe illness and death from the disease, and mRNA vaccine technology has potential applications for other infectious diseases, as well as chronic diseases like cancer. The cancellation removes the bulk of U.S. federal funding for mRNA research, leaving questions about future progress by the U.S. in this area of vaccine technology.
August 15, 2025HHS reinstates the defunct Task Force on Safer Childhood Vaccines.
– The original Task Force on Safer Childhood Vaccines, a federal panel created by Congress in 1986 “to improve the safety, quality, and oversight of vaccines” was disbanded in 1998, but HHS announces that the group will be re-instated at NIH with participation from officials at FDA, CDC, and other government agencies. The goal of the reconstituted Task Force will be “the development, promotion, and refinement of childhood vaccines that result in fewer and less serious adverse reactions than those vaccines currently on the market, and improvements in vaccine development, production, distribution, and adverse reaction reporting” to help increase federal oversight and investigation of vaccine injuries.  The Task Force will come together to develop recommendations to be submitted to Congress within two years, with updates every two years after. Reinstatement of this panel has been a goal of anti-vaccine advocates for years, including the Children’s Health Defense, the anti-vaccine organization Secretary Kennedy founded, which supported a lawsuit earlier in 2025 against Kennedy that sought to require him to reconvene the Task Force.
August 27, 2025FDA approves COVID-19 vaccines for 2025-2026, while limiting scope of approval to certain ages and risk profiles.
– FDA approves updated COVID-19 vaccines for 2025-2026, but also limited the approval to persons 65 and older and those between 18 and 64 with a health condition that puts them at higher risk for severe disease. Previously, the FDA had approved the use of vaccines for all ages (over 6 months) regardless of risk profile.
September 9, 2025MAHA Commission releases strategy to address childhood chronic disease.
– A new MAHA Commission strategy document outlines actions the federal government is taking or plans to take to address childhood chronic disease in the U.S. These include “more than 120 initiatives” that together represent “the most ambitious national effort ever to confront childhood chronic disease,” and which outline a “blueprint for the entire government” to address chronic disease. Elements of the strategy include: changing federal science and research priorities, reforming dietary guidelines, changing nutrition and food regulations through reducing additives and ultra-processed foods, and improving effort to raise public awareness about chronic disease. The strategy highlights the risks of vaccine injuries, fluoride in drinking water, among many other areas.
September 18, 2025Secretary Kennedy renews the declaration of the national opioid crisis as a public health emergency.
– In a declaration on an HHS website, Secretary Kennedy renews the declaration of the opioid crisis as a national public health emergency (PHE).  The opioid crisis was initially declared a public health emergency in 2017; renewal is required every 90 days to continue the PHE.
September 19, 2025Secretary Kennedy announces that the FDA will launch a new review of mifepristone.
– Secretary Kennedy announced that the FDA will undergo a review of the current Risk Evaluation and Mitigation Strategy (REMS) for mifepristone, due to new evidence including an April 2025 report from the Ethics and Public Policy Center (EPPC) which claims that mifepristone has a higher rate of adverse events than previously reported. This report has drawn criticism due to methodological flaws and lack of transparency regarding its data sources.
September 19, 2025ACIP makes several new recommendations related to MMRV and COVID-19 vaccines. 
– In its September 18-19 meeting, ACIP members vote on several new recommendations including to no longer recommend the combination MMRV (measles, mumps, rubella, and varicella) vaccine for children under the age of 4 and instead to recommend that children in this age group receive measles, mumps, and rubella (MMR) vaccine separately from the varicella vaccine (V). In addition, ACIP members vote to change what had been a universal COVID-19 vaccine recommendation (except for HHS’ recent change for healthy children and pregnant women) to “shared clinical decision-making”, including for those 65 and older, along with a recommendation for new language on risk-benefit for COVID-19 vaccinations. ACIP’s recommendations were adopted by CDC on October 6. While the separate MMR+V vaccines had been recommended as preferred by the CDC for many years, the combination MMRV provided an option for parents to reduce the number of injections their children receive. Now, insurers will no longer be required to cover this vaccine at no-cost. The new COVID-19 vaccine recommendations mean people of all age groups are now recommended to have an interaction with a health care provider (which could include a doctor, nurse, or pharmacist) to determine whether getting a COVID-19 vaccination is recommended for them. If that determination is made, insurers must cover the vaccine at no-cost, although it is possible that some consumers may face challenges in accessing providers in the first place or demonstrating that they have consulted with a medical provider seeking vaccination in some cases.    
September 22, 2025President Trump and Secretary Kennedy announce new actions to address autism spectrum disorder in the U.S.
– In a press conference and via an HHS press statement and Fact Sheet, President Trump and HHS Secretary announce several actions to address the issue of autism spectrum disorder (ASD) in the U.S. This includes FDA authorization for leucovorin, a treatment option for some children with autism, a regulatory change that will allow state Medicaid programs to newly cover leucovorin for the indication of ASD. President Trump and Secretary Kennedy also highlight what they say are risks of acetaminophen use during pregnancy and association with autism. The press release notes “HHS wants to encourage clinicians to exercise their best judgment in use of acetaminophen for fevers and pain in pregnancy by prescribing the lowest effective dose for the shortest duration when treatment is required.”  In his remarks, President Trump also implicated childhood vaccines as a potential risk factor for autism, though no new evidence was presented and that link has already been repeatedly and conclusively ruled out. In a subsequent press statement on September 22, HHS announced FDA was initiating a labeling change for leucovorin, and a safety label change for acetaminophen to include information about the “potential risks of acetaminophen so patients can make a more informed decision.” Public health groups and experts criticized the conclusions linking acetaminophen use in pregnancy and autism, and expressed doubts about leucovorin as a treatment for autism. President Trump’s remarks also precipitated a lawsuit filed on October 28 in Texas against the maker of Tylenol.
September 30, 2025FDA approves a new generic mifepristone product.
– The FDA approved Evita’s Solutions application for a generic version of mifepristone.   The approval included a reminder that the generic mifepristone is subject to the same  Risk Evaluation and Mitigation Strategy (REMS) as the brand-name.
September 30, 2025HHS awards $60 million in grants to support prevention of falls and related programs for older adults and those with disabilities.
– Secretary Kennedy announced 59 new grants totaling $60 million is being awarded to states, territories, tribes, and local organizations supporting older adults and Americans with disabilities, including programs for “preventing falls among seniors, managing chronic conditions…and funding dementia-capable programs.”
October 10, 2025Trump Administration fires thousands of HHS employees, including hundreds at CDC, during federal government shutdown.
– In the midst of a government shutdown and an ongoing federal funding impasse in Congress, the White House Office of Personnel and Management says over 4,000 federal workers are to be fired. At HHS, over a thousand workers are notified that they have lost their jobs, with most of those losses concentrated at CDC. Some of those job losses were reversed over the next few days, with HHS officials stating some notices were sent in error. Even so, as of October 14 it is estimated that about 600 CDC employees remain fired, including staff in areas such as injury prevention, health statistics, and Congressional relations. There is a question about whether such firings during a government shutdown are legal, and groups representing federal workers have filed lawsuits to halt these mass layoffs.
October 31, 2025FDA announces new restrictions on ingestible fluoride products for children.
– FDA announces new enforcement actions “to restrict the sale of unapproved ingestible fluoride products for children” and sends letters to health care professionals warning about the risks associated with these products. The actions come after FDA conducted a review and published a scientific evaluation of these products. In the announcement. FDA says it will be developing a “fluoride research agenda” and “the first national oral health strategy” for the U.S. in partnership with NIH and other HHS agencies.
November 10, 2025FDA announces a warning label change on hormone replacement therapy (HRT) products for addressing symptoms of menopause.
– In a press release, a fact sheet, and a live press event, FDA leaders announce that they will initiate the removal of broad “black box” warnings from HRT products for menopause. The FDA also announces approvals for two new drugs for menopausal symptoms. According to the FDA, women have been “under-utilizing approved therapies” since the “black box” warnings about risks associated with the drugs were placed on these products over 20 years ago. Labels will be rewritten with guidance saying that there are long-term health benefits if HRT is begun within 10 years of the onset of menopause.
November 19, 2025CDC changes language on its website to say a link between vaccines and autism cannot be ruled out.
– A CDC website providing information to the public on Autism and Vaccines, is changed to include language saying “studies have not ruled out the possibility that infant vaccines cause autism.” The new site also discusses the “state of the evidence” on common childhood vaccines and supposed links to autism. The new language is a reversal from previous CDC statements saying “vaccines do not cause autism,” and contradicts the long established scientific consensus that there is no link between vaccines and autism. The new CDC webpage language has been criticized by professional medical organizations such as the American Medical Association and the American Academy of Pediatrics, as well as autism organizations such as Autism Speaks and the Autism Science Foundation.
November 21, 2025CDC staff ordered to end all monkey research programs, potentially affecting development of prevention tools for HIV and other infectious diseases.
– According to reports, CDC staff are ordered to halt its monkey research program by the end of 2025. This program has helped develop HIV prevention tools such as pre-exposure prophylaxis (PrEP) and microbicides, as well supported prevention research for other infectious diseases.
November 28, 2025Internal FDA communication proposes stricter federal requirements for testing and approving vaccines.
– According to reports, the head of FDA’s Center for Biologics Evaluation and Research (CBER), which is responsible for regulating vaccines, issues an email to staff proposing new, stricter federal requirements for vaccine testing, evidence, and approval. The email states that in the future FDA will “demand pre-market randomized trials assessing clinical endpoints for most new products” and that FDA “will not be granting marketing authorization to vaccines in pregnant women” without this kind of evidence. Newly developed pneumonia, influenza, and COVID-19 vaccines are specifically mentioned as vaccines that would be subject to these new requirements. The rationale given for this policy change is a new analysis of vaccine safety data indicating “COVID-19 vaccines have killed American children,” though no evidence to support that statement is provided in the email.
December 5, 2025ACIP votes to end recommendation that all newborns receive hepatitis B vaccine dose at birth
On the second day of the Advisory Committee on Immunization Practices’ (ACIP) December 4-5 meeting, members vote to end a long-standing recommendation that all newborns in the U.S. receive a dose of hepatitis B vaccine. The committee now recommends parents of infants born to mothers who test negative for hepatitis B consult with their provider to help decide if and when their child should receive the first hepatitis B dose. ACIP continues to recommend that infants born to mothers who test positive for hepatitis B, or whose hepatitis B test status is unknown, receive the first hepatitis B vaccine dose at birth. A recommendation from ACIP becomes part of the official CDC immunization schedule once it is adopted by the CDC director.
December 30, 2025HHS ends certain requirements for state reporting of immunization data to the Centers for Medicare and Medicaid Services (CMS).
A December 30 letter from the Centers for Medicare and Medicaid Services (CMS) informs state health officials that starting in 2026, states will no longer be required to report several measures related to immunization status to CMS. Specifically, CMS removes the following from its “Child and Adult Core Sets”: “Childhood Immunization Status”, “Immunizations for Adolescents”, “Prenatal Immunization Status: Under Age 21”; and “Prenatal Immunization Status: Age 21 and Older.” In addition, in its letter CMS informs state health officials it will “explore options to facilitate the development of new vaccine measures that capture information about whether parents and families were informed about vaccine choices, vaccine safety and side effects, and alternative vaccine schedules” and “how religious exemptions for vaccinations can be accounted for.” Data reported by states and included in the Child and Adult Core Sets are used by Medicaid and CHIP to monitor access to and quality of health care for their beneficiaries, so an absence of this data could make monitoring immunization coverage in this population more challenging.
January 5, 2026HHS announces changes to the federal childhood vaccination schedule that reduce the number of routinely recommended vaccines
Health and Human Services (HHS) issues a memo implementing major changes to the government’s recommended vaccination schedule for children. Under the new guidelines, there are vaccines for 11 diseases recommended for all children, down from 17 diseases a year ago. In addition to COVID-19 (which HHS stopped recommending for all children back in October 2025), the new schedule no longer recommends routine vaccinations for five other diseases: rotavirus, COVID-19, influenza, hepatitis A, hepatitis B, and meningococcal. These vaccines have been moved from routine recommendation to “shared clinical decision making,” a process that is “individually based and informed by a decision process between the health care provider and the patient or parent/guardian.”  The HPV vaccine remains recommended for routine vaccinations, though under the new guidelines HHS reduces the number of recommended doses of HPV drops from two or three (depending on age of initial vaccination) to one. Coverage for all of these immunizations should remain the same through public and private insurance mechanisms. On March 16, 2026, a federal judge issued a ruling that stayed changes to the vaccine schedule from being implemented, as the government did not follow required procedures. On April 29, HHS appealed the judge’s stay and court review continues.
February 3, 2026BARDA opens solicitations for a $100 million prize program for development of novel antivirals targeting dengue, West Nile, and other viruses.
In a news release, HHS’ Biomedical Advanced Research and Development Authority (BARDA) announces it is opening solicitations for a share of a new $100 million SMART Antiviral prize intended to speed the development of “broad-spectrum, small-molecule antiviral therapies” targeting families of viruses that include dengue, Zika, West Nile, and Chikungunya. This first stage is designed to receive solicitations at the concept stage, with solicitations for further development stages anticipated in the future.
February 4, 2026Trump Administration instructs CDC to rescind $600 million in public health funds going to four Democratic-led states
According to reports, the Office of Management and Budget ordered CDC to cut $600 million in funding that had been earmarked for state and local public health programs in California, Colorado, Illinois, and Minnesota. Most of the funding cuts affect programs focused on HIV and STD prevention, are are to be terminated because they “do not reflect agency priorities” according to an HHS spokesperson. On February 11, affected states filed a lawsuit in federal court against these cuts, and on February 12 a federal judge issued a temporary restraining order blocking the cuts from taking effect.
February 10, 2026FDA refuses to review Moderna’s license application for its investigational mRNA-based influenza vaccine
Moderna announces it received a “Refusal to File” letter from FDA stating that the agency will not initiate a review of the company’s biological license application for its investigational mRNA-based seasonal influenza vaccine. According to FDA, the refusal is due to the company’s use of an inadequate comparison arm in its study. Moderna states the letter is “inconsistent with previous written communications” with FDA staff. On February 18, Moderna announced that FDA had reversed its decision, and will now review the application, following further discussions with the company.
February 18, 2026FDA to allow drug approvals with evidence from one clinical trial rather than two
In an opinion article published in the New England Journal of Medicine, FDA leaders announce a new FDA policy that will make the default requirement for FDA approvals to be results from one clinical trial instead of the prior requirement of two clinical trials.  The stated goal of the change is to accelerate the approval and availability of new medicines.
February 19, 2026CDC delays February ACIP meeting
HHS/CDC announces the ACIP meeting previously scheduled for February 25-27 will be postponed. The postponement occurs amid an ongoing federal lawsuit filed by the American Academy of Pediatrics (AAP) and other medical groups that argues the recent revisions made by HHS to the federal child immunization schedule were arbitrary and violated administrative procedures and seeks to have the ACIP panel appointed by HHS Secretary Kennedy removed and replaced and its decisions overturned. On February 26, CDC announced the ACIP meeting had been rescheduled for March 18-19. On March 16, 2025, the judge ruled that 13 of 15 ACIP member appointments did in fact violate administrative procedures and their appointments are stayed along with any ACIP votes since the appointments were made. As a result, the planned March 18-19 ACIP meeting has been canceled.
February 23, 2026FDA launches new framework for speeding development and approval of therapies for rare diseases
FDA announces draft guidance for drug developers that seek approval for targeted, individualized therapies. The new framework outlines new approaches to regulatory review and evidence requirements on the safety and efficacy for rare diseases, given that traditional randomized clinical trials may not be feasible for these conditions.
March 4, 2026HHS Postpones Third Straight Meeting of US Preventive Services Task Force (USPTF)
USPTF, which makes recommendations on preventive health care services, has not met since March of 2026. Five of the 16 USPTF members’ terms have ended as of January 1 and have not been replaced.  
April 10, 2026HHS Publishes Updated ACIP Charter
The Trump Administration published an updated version of the Advisory Committee on Immunization Practices (ACIP) charter. The revised charter features language that broadens the inclusion criteria for ACIP member expertise, including mentions of vaccine safety and recovery from serious vaccine injuries as areas of expertise that members can possess.  The charter language was updated yet again in May, with the newest version published on May 27, 2026. The newest version places oversight of ACIP more directly under the CDC director, includes language that emphasizes potential gaps or limitations in vaccine data, and does not commit to a set schedule of ACIP meetings annually (previously, the charter required three ACIP meetings a year).
April 22, 2026CDC Study on COVID-19 Vaccine Effectiveness Held Back From Publication
Reports find that Jay Bhattacharya, who is overseeing CDC operations while the Director position remains unfilled, held back publication of a CDC study on the effectiveness of the COVID-19 vaccine over the 2025-2026 winter season. The study was scheduled to be published in the CDC’s flagship MMWR publication on March 19, but Bhattacharya objected to the study’s design, although it is a very common design that has been used to study vaccine effectiveness in dozens of prior published studies. The study had found vaccination cut the likelihood of emergency visits due to Covid by 50 percent and of hospitalizations by 55 percent. Eventually, the study was published in a different journal in June 2026.
May 29, 2026 Executive Order On Childhood Vaccines Directs HHS to Review and Update U.S. Childhood Vaccine Schedule
The White House issues an executive order titled “Realigning United States Core Childhood Vaccine Recommendations with Best Practices from Peer, Developed Countries” that instructs federal agencies, including HHS, that the childhood vaccine schedule “should be aligned with scientific evidence and best practices from peer, developed countries while preserving access to vaccines currently available to Americans.” This follows an earlier memorandum from December 5, 2025 instructing HHS to align the childhood vaccine schedule with that of “peer, developed nations.”
June 18, 2026FDA Advisory Committee Unanimously Recommends Approval of mRNA Influenza Vaccine
The Food and Drug Administration’s (FDA’s) Vaccines and Related Biological Products Advisory Committee (VRBPAC) votes unanimously to recommend approval of Moderna’s mRNA vaccine candidate for older adults. In February of this year FDA had said it would not review Moderna’s application for this vaccine, but several weeks later reversed course and agreed to review after Moderna proposed a revised approach to regulatory review. The FDA reports it is likely to make its decision on this vaccine by August 5 this year.
June 30, 2026Secretary Kennedy Terminates COVID-19 Emergency Use Authorization Declarations for Drugs, Biological Products, and Medical Devices
HHS announces Secretary Kennedy has terminated COVID-19 Emergency Use Authorization (EUA) declarations for drugs and biological products and for medical devices after determining these authorizations are no longer needed. The declaration for drugs and biological products will terminate 12 months after the Secretary’s determination, while the declarations for medical devices will terminate 180 days after the Secretary’s determination. EUAs for COVID-19 vaccines had already been terminated.
August 10, 2026Executive Order on Vaccines Instructs HHS and States to Realign Childhood Vaccine Recommendations
The White House releases a new Executive Order (EO) titled “Delivering Gold Standard Childhood Vaccine Recommendations for Americans” that states U.S. childhood vaccine recommendations should be “aligned with scientific evidence and best practices from peer, developed countries,” and sets out three categories of recommended immunization (echoing the January 5 HHS memo described above that issued a new federal childhood vaccine schedule, which has been put on hold by a federal judge). The new EO also directs the HHS Secretary to offer some childhood vaccines such as measles, mumps, and rubella (MMR) as “single vaccines rather than combination products,” and to align vaccine recommendations with findings to be released by a federal panel known as the “HHS Task Force on Safer Childhood Vaccines.”
September 17, 2026HHS Secretary Names Eight New Members of the U.S. Preventive Services Task Force
Secretary of HHS Robert F. Kennedy Jr. names eight new members of the U.S. Preventive Services Task Force (USPSTF), a panel of experts with responsibilities to assess evidence and make recommendations regarding many preventive medical services. The panel has not been convened since March 2025.
September 14, 2026HHS Institutes New Approach to Counting Deaths in Official CDC Measles Tally
Following a public dispute between Governor of Pennsylvania Josh Shapiro and HHS Secretary Robert F. Kennedy, Jr. regarding deaths in the state attributable to measles, HHS states it will take new approach for counting deaths in official CDC statistics about the current measles epidemic in the U.S. Instead of relying on state and local health departments’ reports of measles deaths as was done previously, HHS will now review each each reported case and look to mortality reports and death records collected and analyzed via the National Center for Health Statistics (NCHS). On its measles page, CDC now includes a note saying “CDC will update its reporting [of the number of measles deaths] as additional information becomes available and relevant reviews are completed.” As of October 12, 2026 the state of Pennsylvania has reported six total measles-associated deaths while the CDC page counts two measles deaths only.
October 8, 2026HHS Launches Agency-Wide Actions Focused on Vaccine Injuries
In an announcement, HHS states it is launching a number of actions across the agency focused on vaccine injuries intended “to strengthen how the federal government identifies, documents, investigates, and responds to health problems reported following vaccination.” These actions include opening a new clinic located at NIH “dedicated to studying and caring for patients experiencing health problems following vaccination,” issuing a new proposal to reimburse physicians “for the time they spend submitting reports of suspected vaccine-related injuries to VAERS [the Vaccine Adverse Events Reporting System],” and modernizing VAERS through making the system accessible on mobile devices and improving tools for research using VAERS data.

Nearly Three-Quarters of Medicare Advantage Enrollees Could be Denied a Medigap Policy Due to a Pre-Existing Condition

Published: Oct 13, 2026

People with Medicare can choose to receive their Medicare benefits through either traditional Medicare or Medicare Advantage, and this choice poses tradeoffs. In traditional Medicare, beneficiaries may see any doctor or hospital that accepts Medicare, generally without needing a referral or prior authorization. However, traditional Medicare includes relatively high cost sharing and there is no cap on out-of-pocket spending, potentially exposing beneficiaries to very high costs. Most people who enroll in traditional Medicare have an additional source of coverage to help with these costs, including employer coverage, Medicaid, or Medigap. Alternatively, in Medicare Advantage, beneficiaries have an out-of-pocket cap and often reduced cost sharing, but may face more limited provider networks and greater use of prior authorization. Beneficiaries may prefer to switch between sources of coverage as their medical needs and financial circumstances change over time.

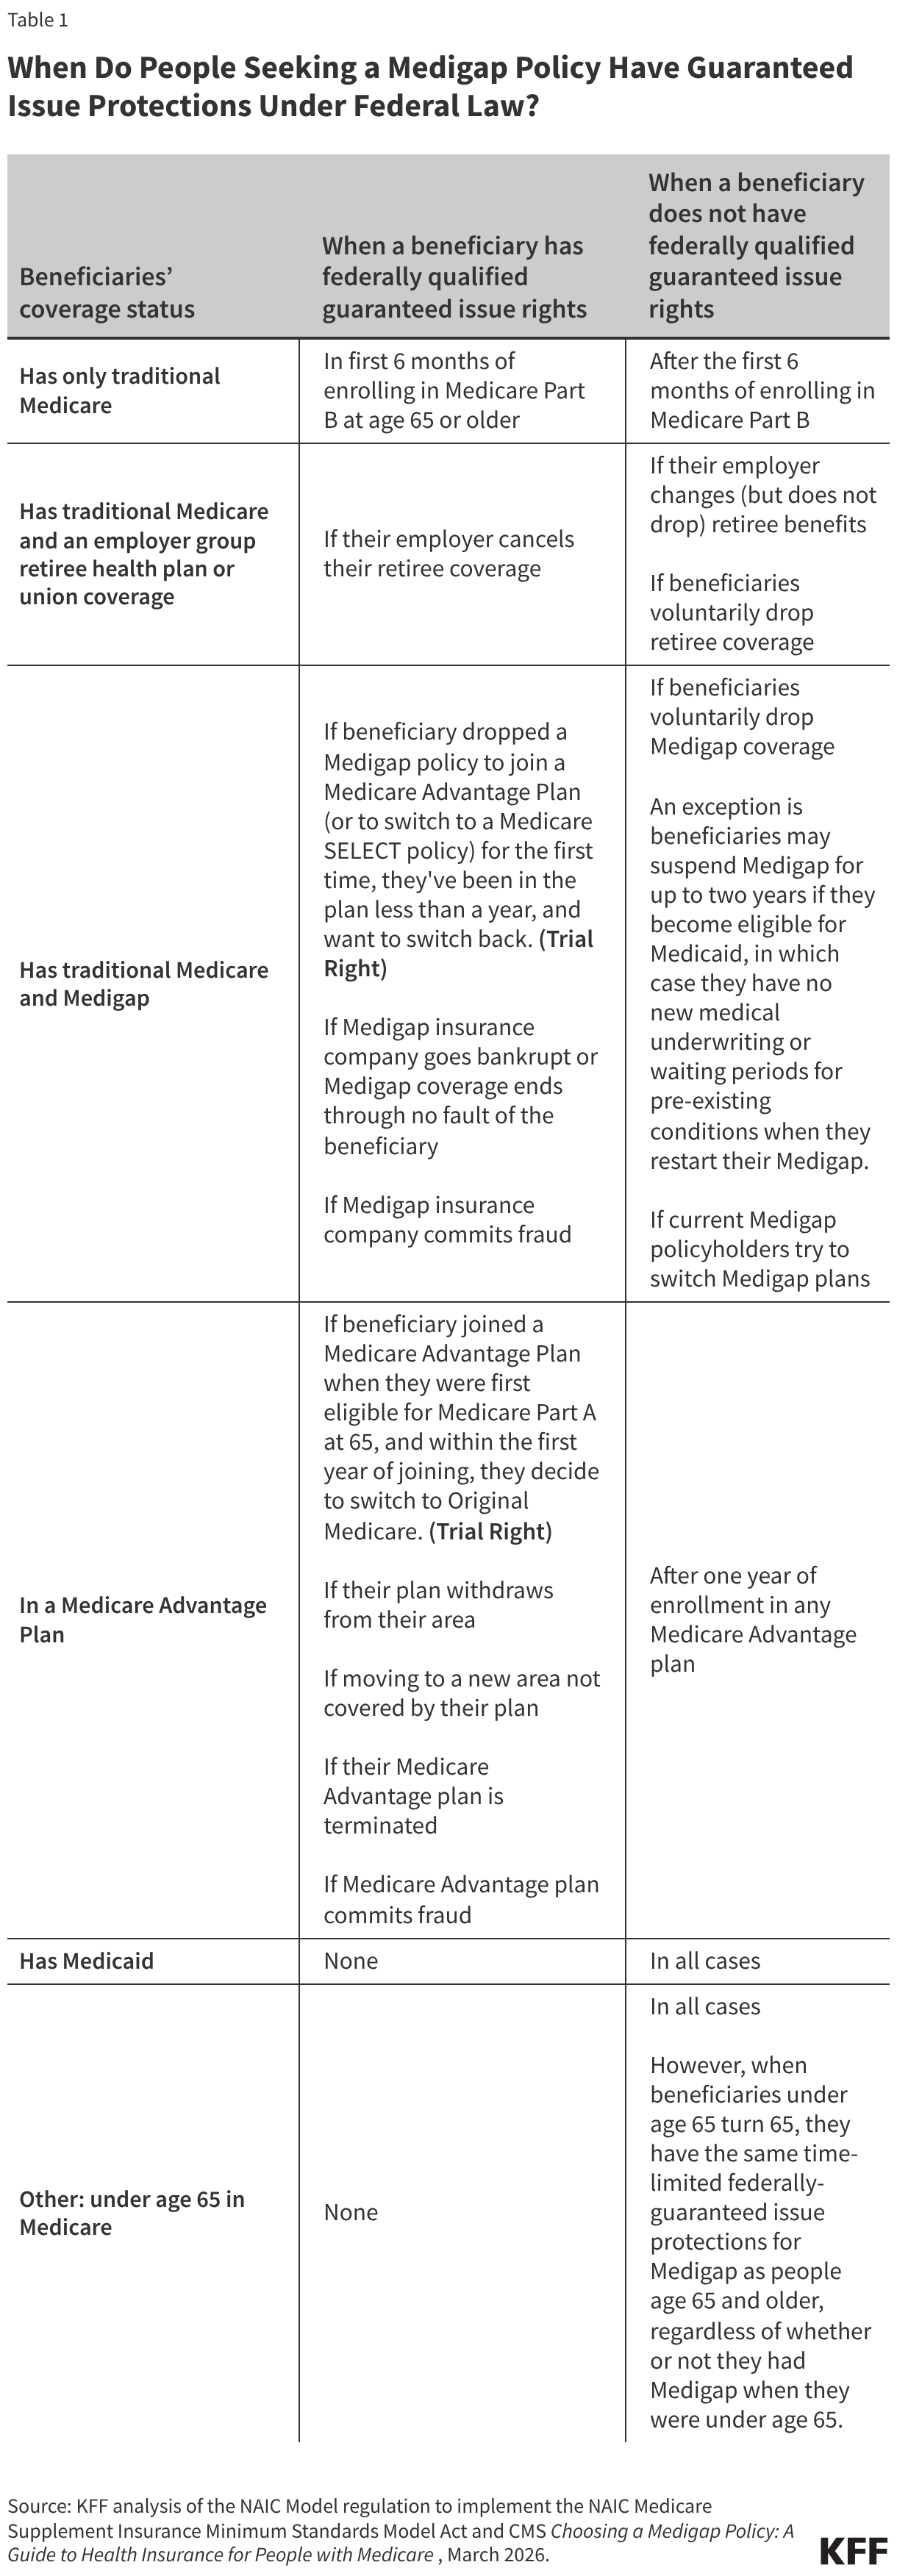
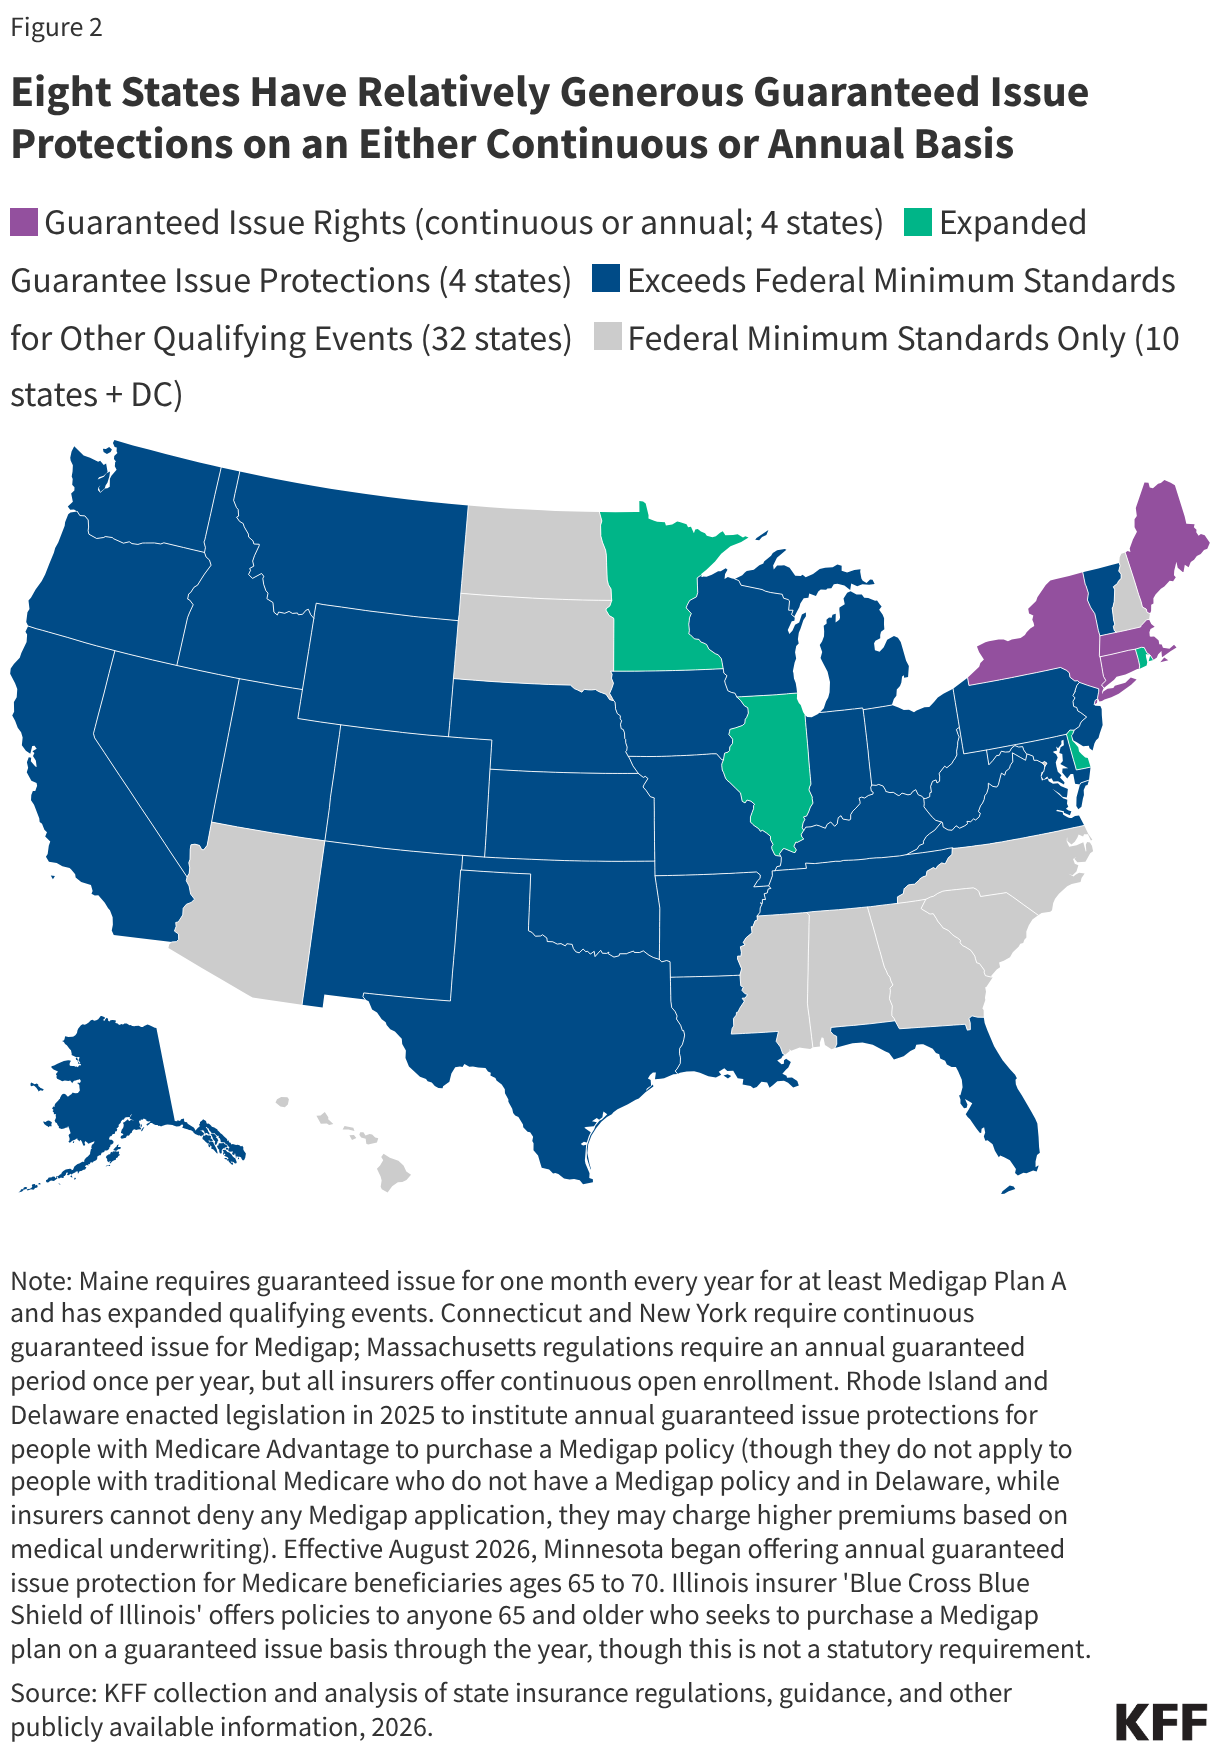
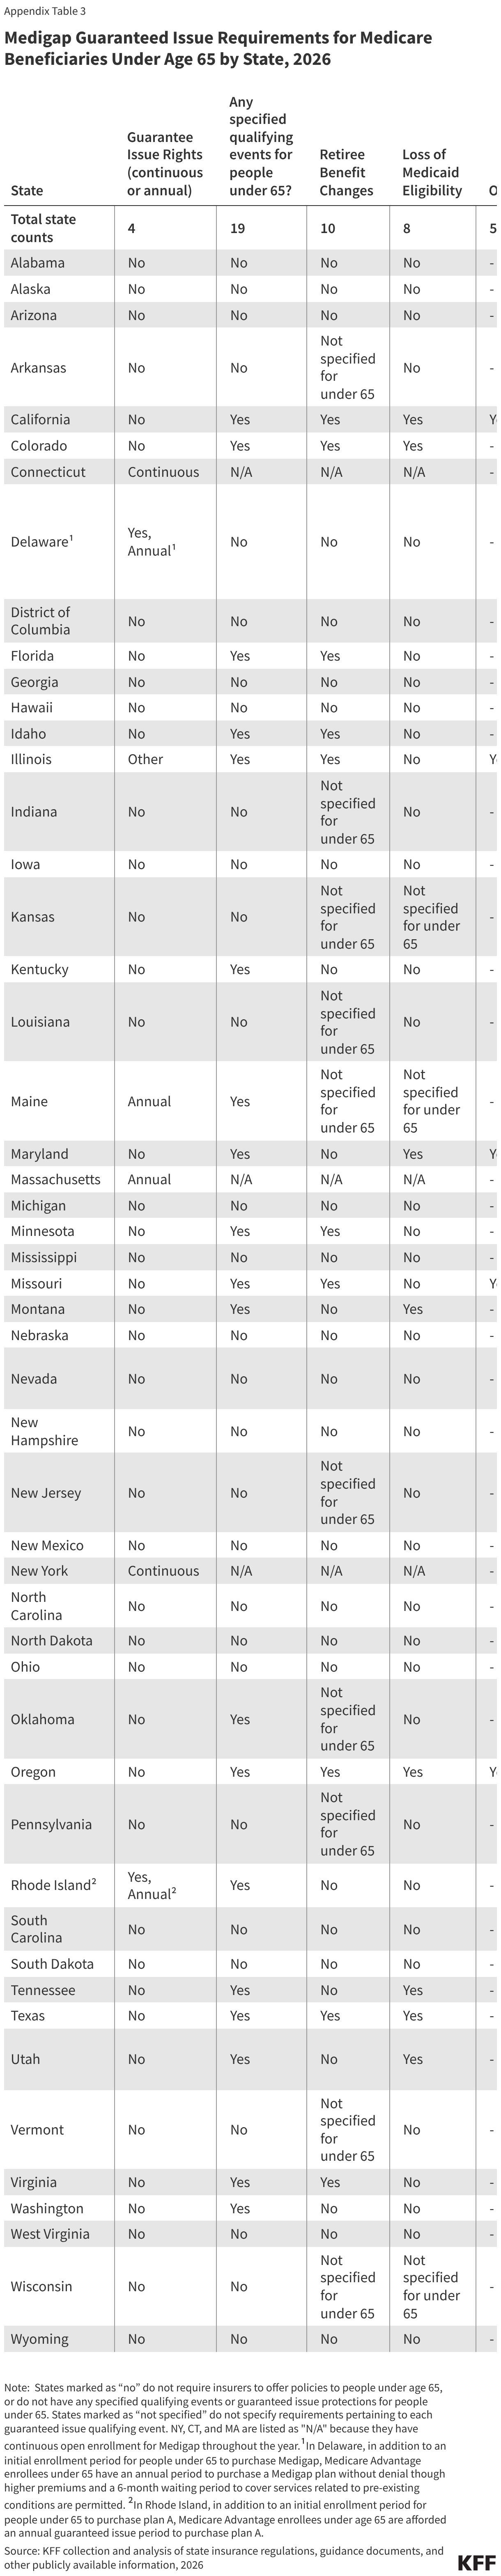
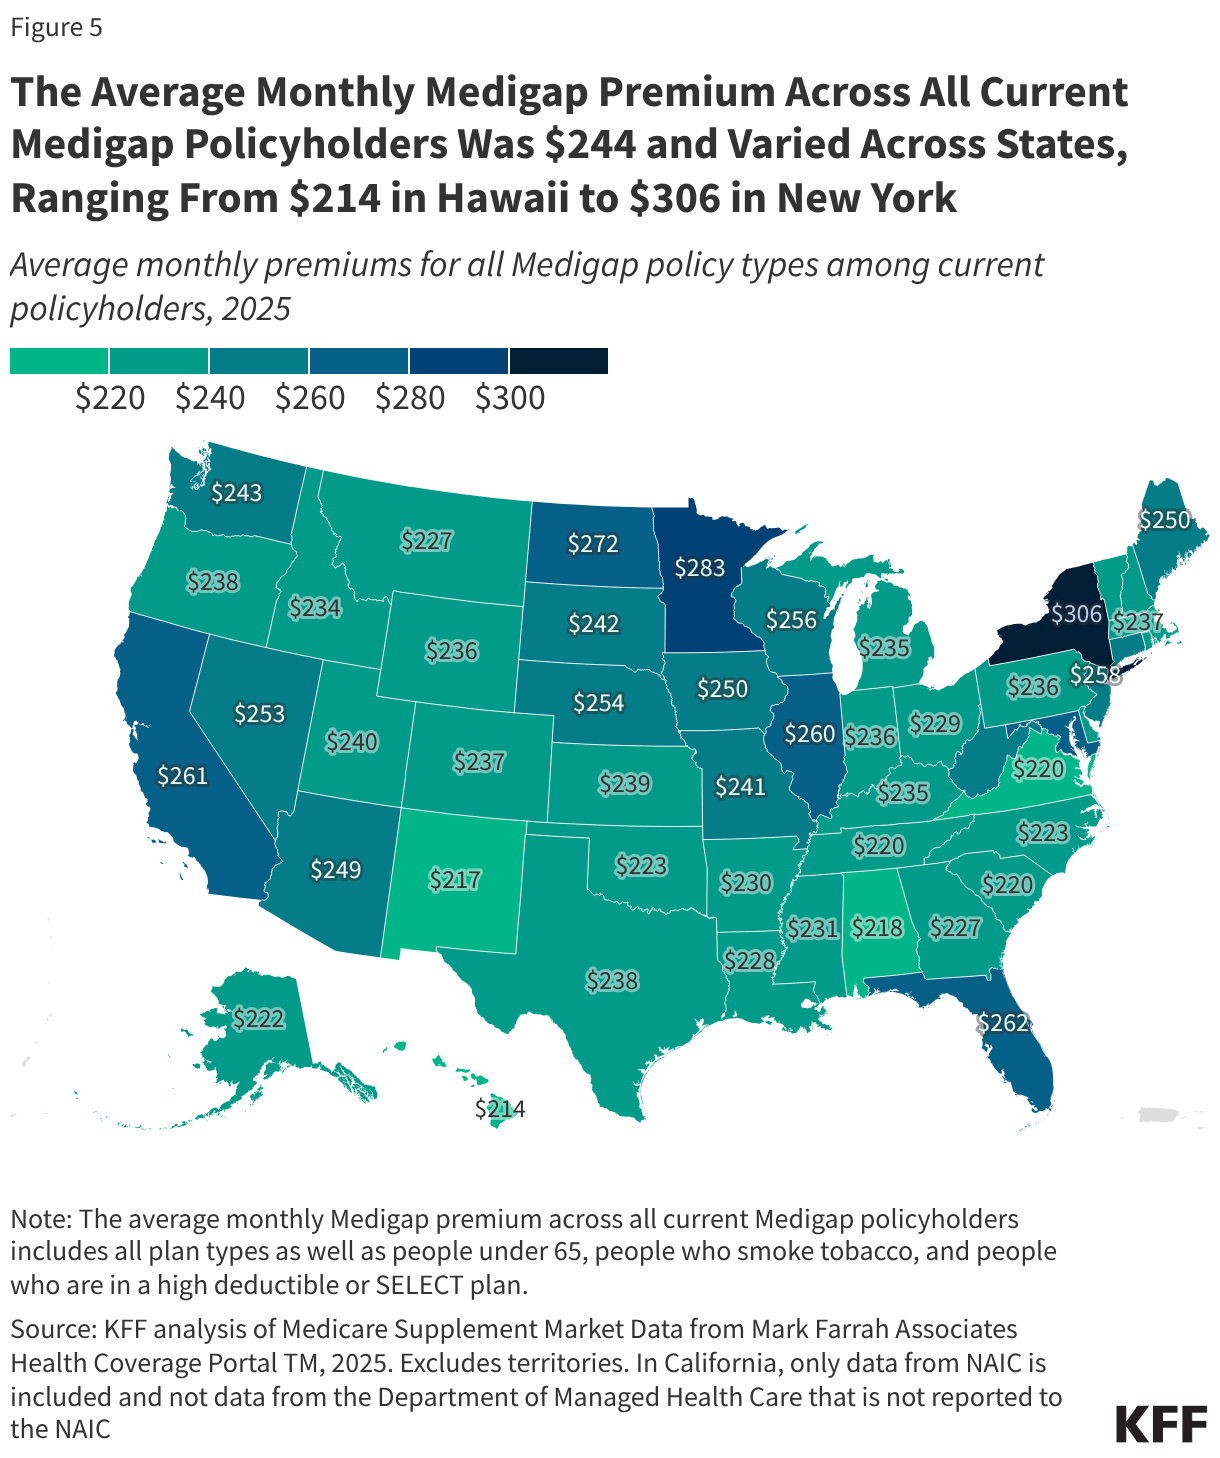
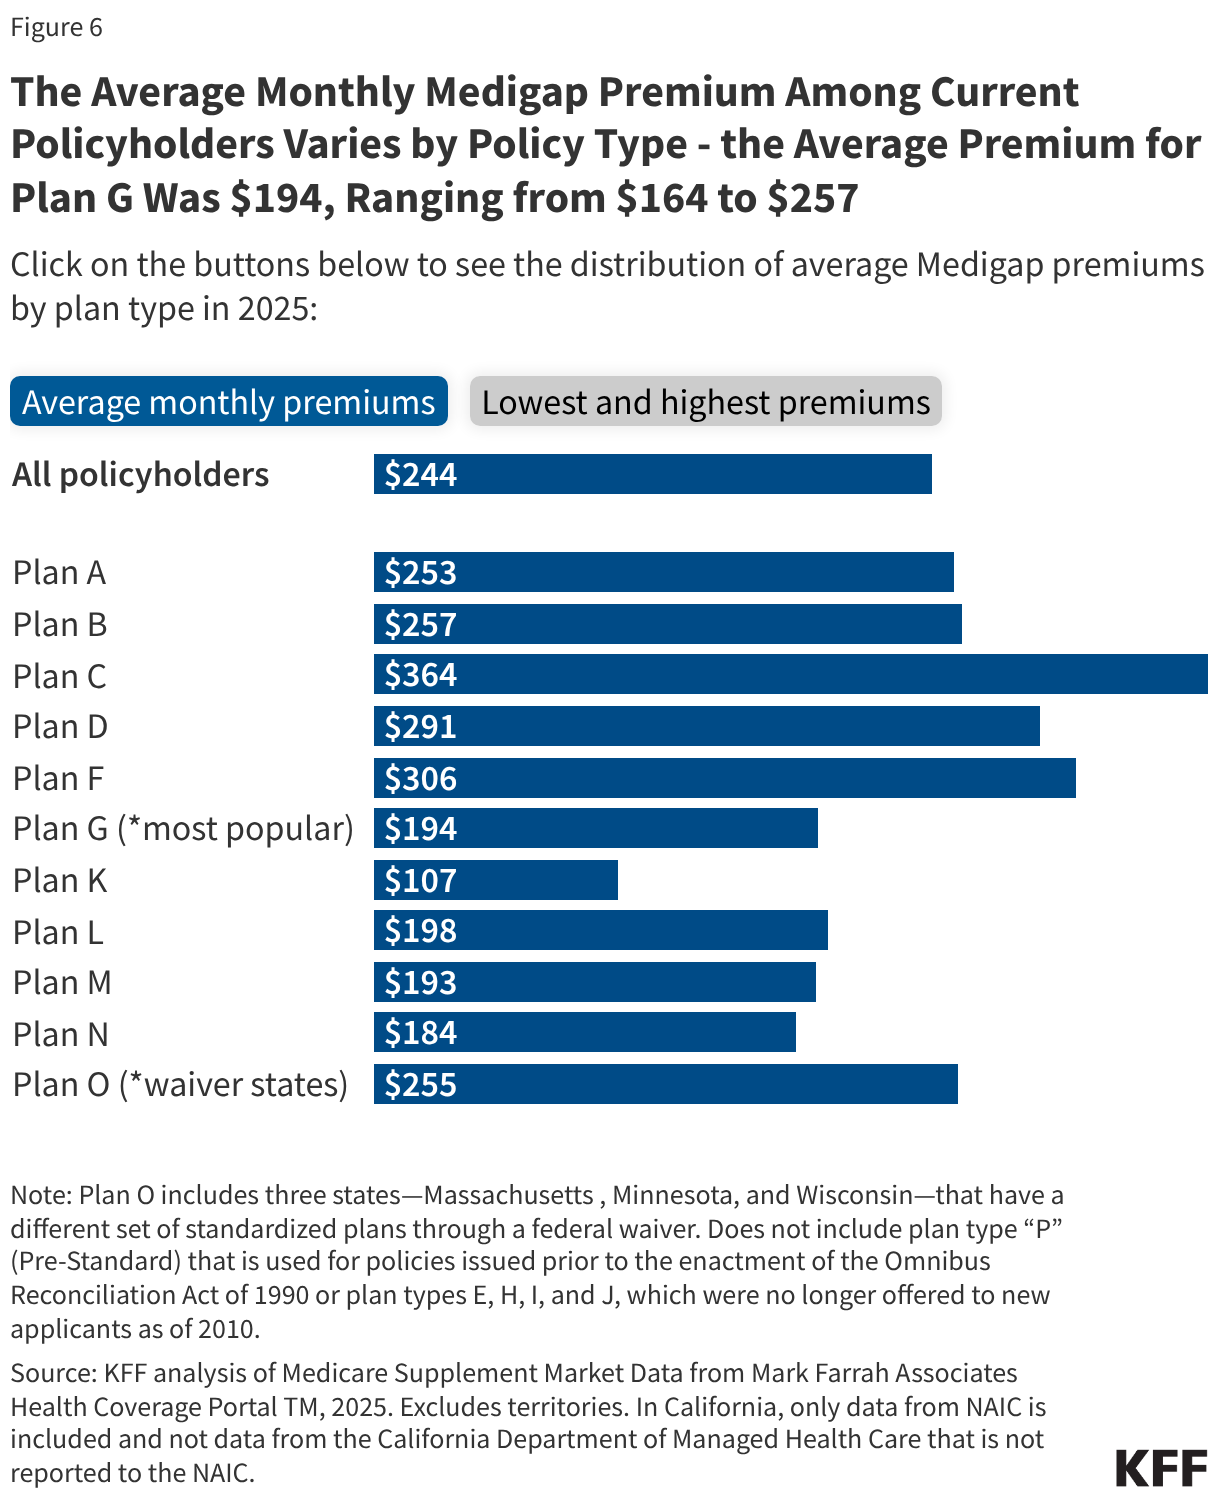
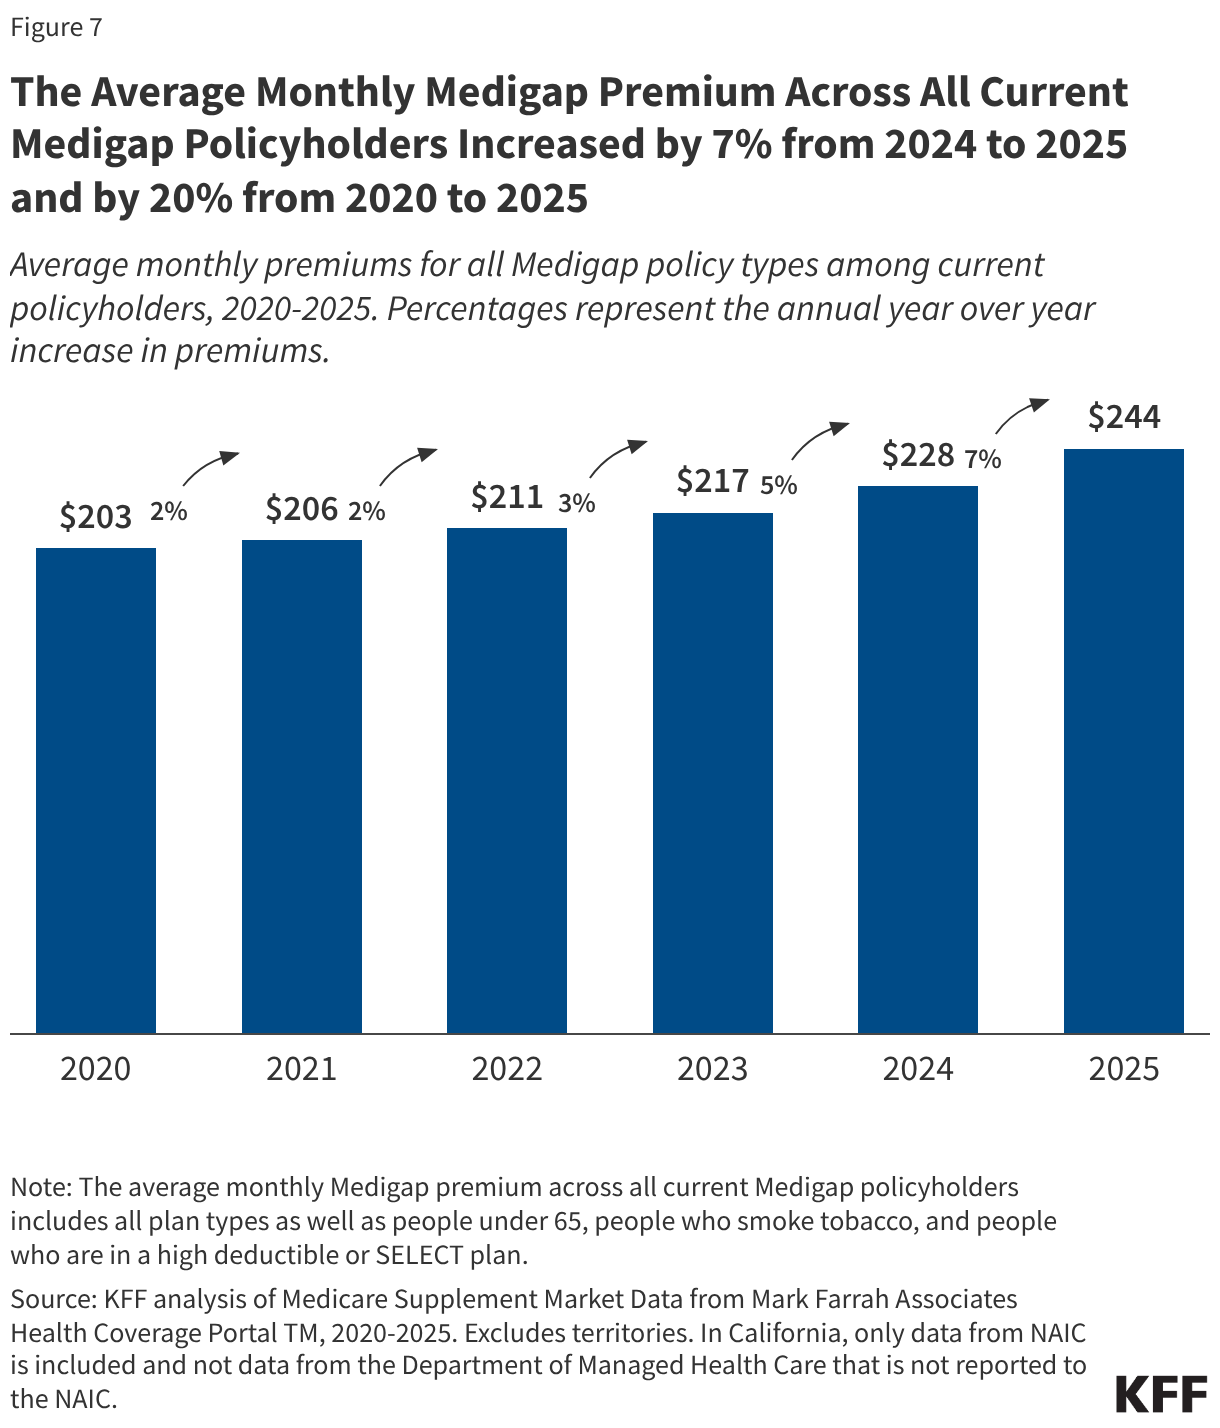
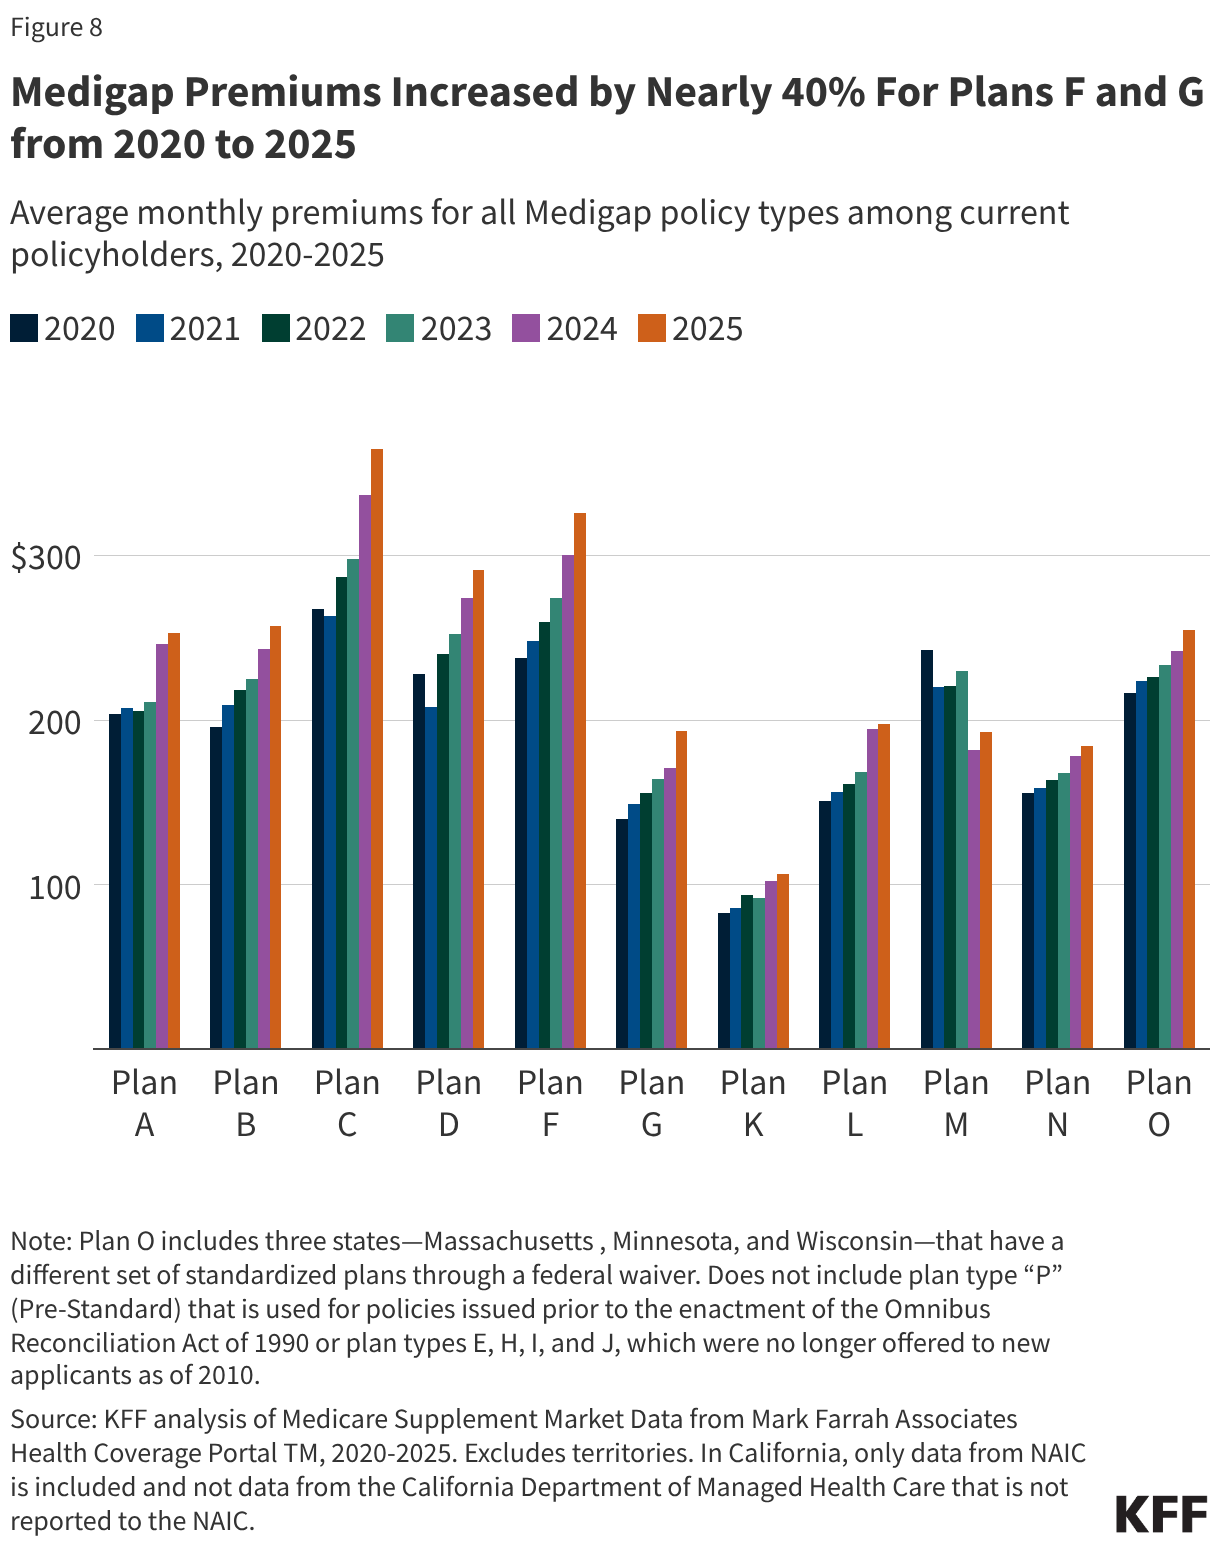
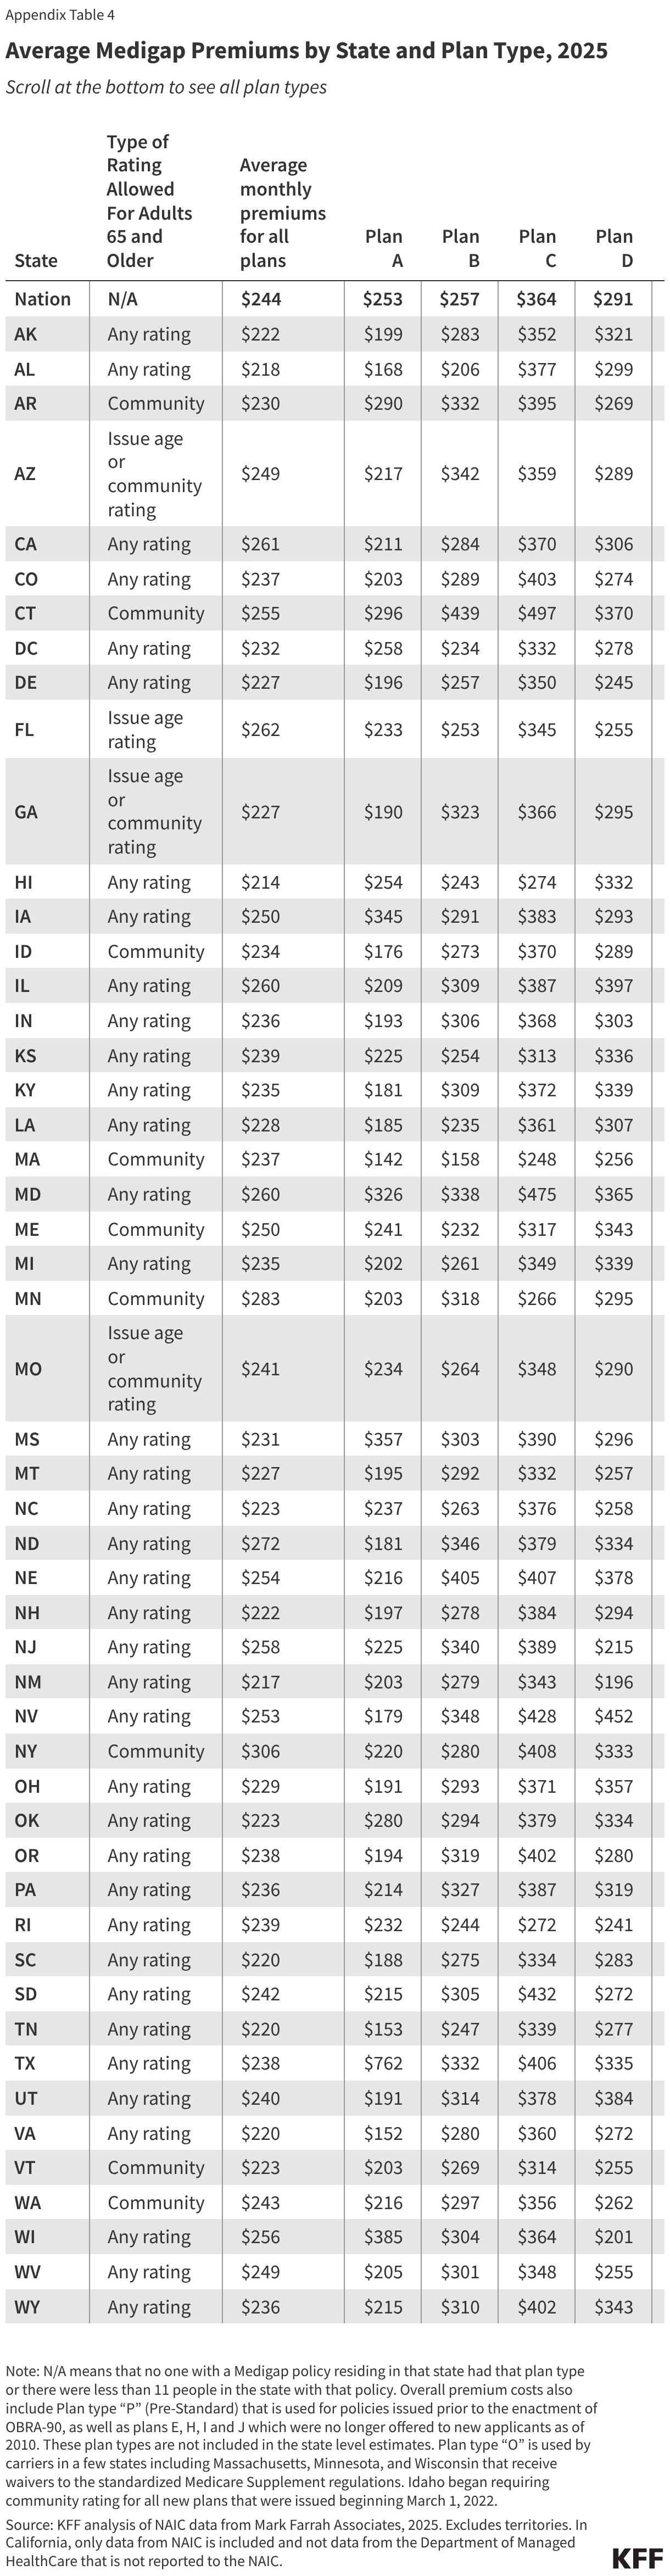
Medigap, which is supplemental insurance sold by private companies, is the most common source of supplemental coverage for people in traditional Medicare. Medigap helps cover Medicare Part A and B cost-sharing requirements, including deductibles, copayments, and coinsurance, with monthly premiums averaging $244 in 2025 among current Medigap policyholders. Federal law provides a one-time, six-month Medigap open enrollment period when beneficiaries age 65 and older first enroll in Part B, during which insurers cannot deny someone a policy or charge them higher premiums due to their to medical history. Additionally, some states provide additional guaranteed issue opportunities for beneficiaries to purchase Medigap without regard to their pre-existing medical conditions (see Box 1).

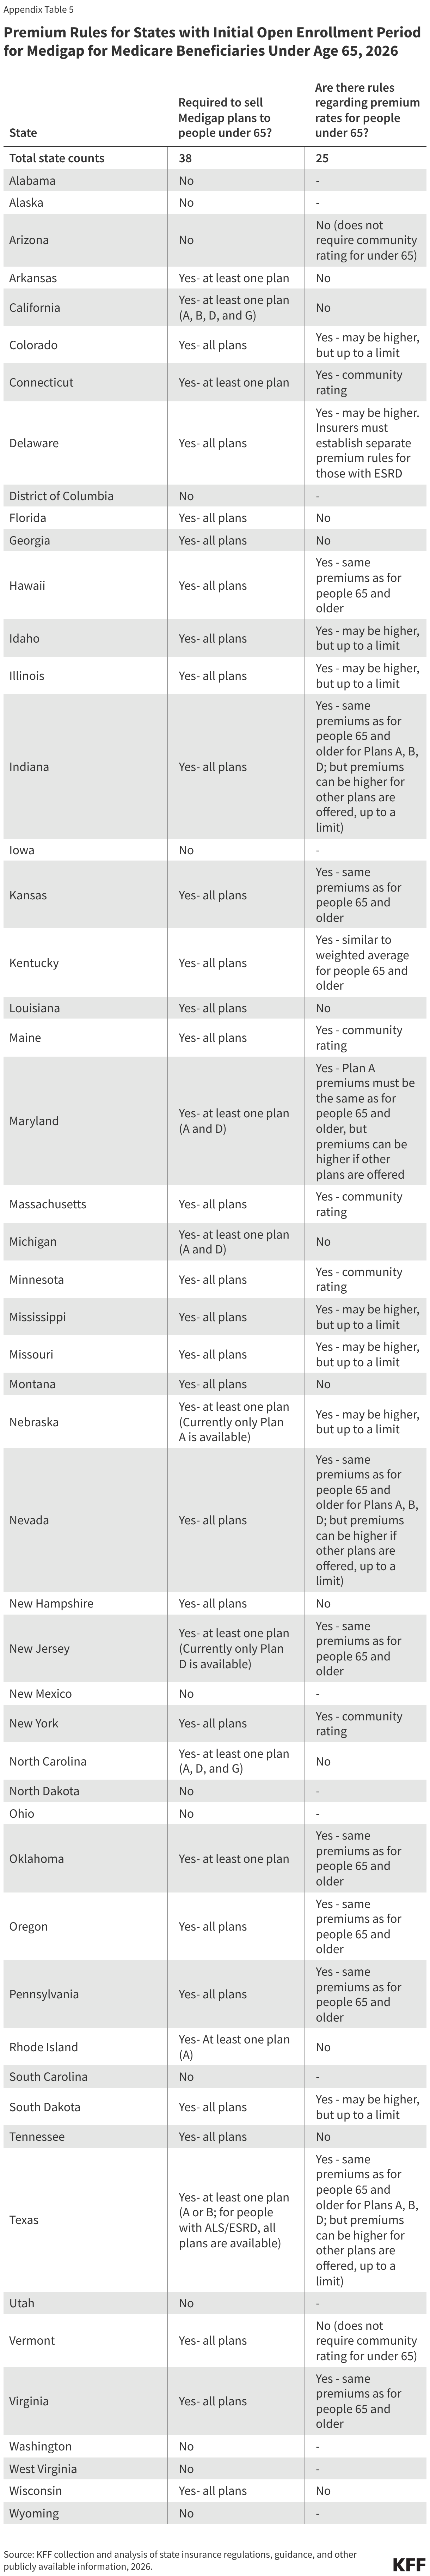
However, outside of this initial enrollment period and other specified circumstances, including a 12-month Medicare Advantage trial period for new enrollees, Medigap insurers are allowed to use medical underwriting when issuing Medigap policies and can charge higher premiums or deny coverage to applicants with pre-existing conditions. These limitations can make it more costly or even impossible for Medicare Advantage enrollees with pre-existing conditions to switch to traditional Medicare and buy a Medigap policy, constraining Medicare beneficiaries’ coverage choices.

This analysis examines the share of Medicare Advantage enrollees who have a pre-existing condition that could result in a Medigap denial if they seek to switch to traditional Medicare outside their one-time 12-month trial period, including national estimates and estimates by age and by state. The pre-existing conditions included in the analysis are based on a KFF review of Medigap applications, which list conditions subject to medical underwriting. The analysis uses Medicare Advantage encounter data for all Medicare Advantage enrollees, including those in individual plans available for general enrollment, employer plans, and special needs plans. This analysis includes dual-eligible individuals, who do not require Medigap as long as they have Medicaid coverage but would potentially be subject to underwriting for Medigap if they lose their Medicaid eligibility. This analysis also includes Medicare Advantage enrollees under age 65, who do not have federal guaranteed issue rights to purchase Medigap, but can take advantage of the initial Medigap open enrollment period when they turn 65 (see Methods for more detail).

Takeaways

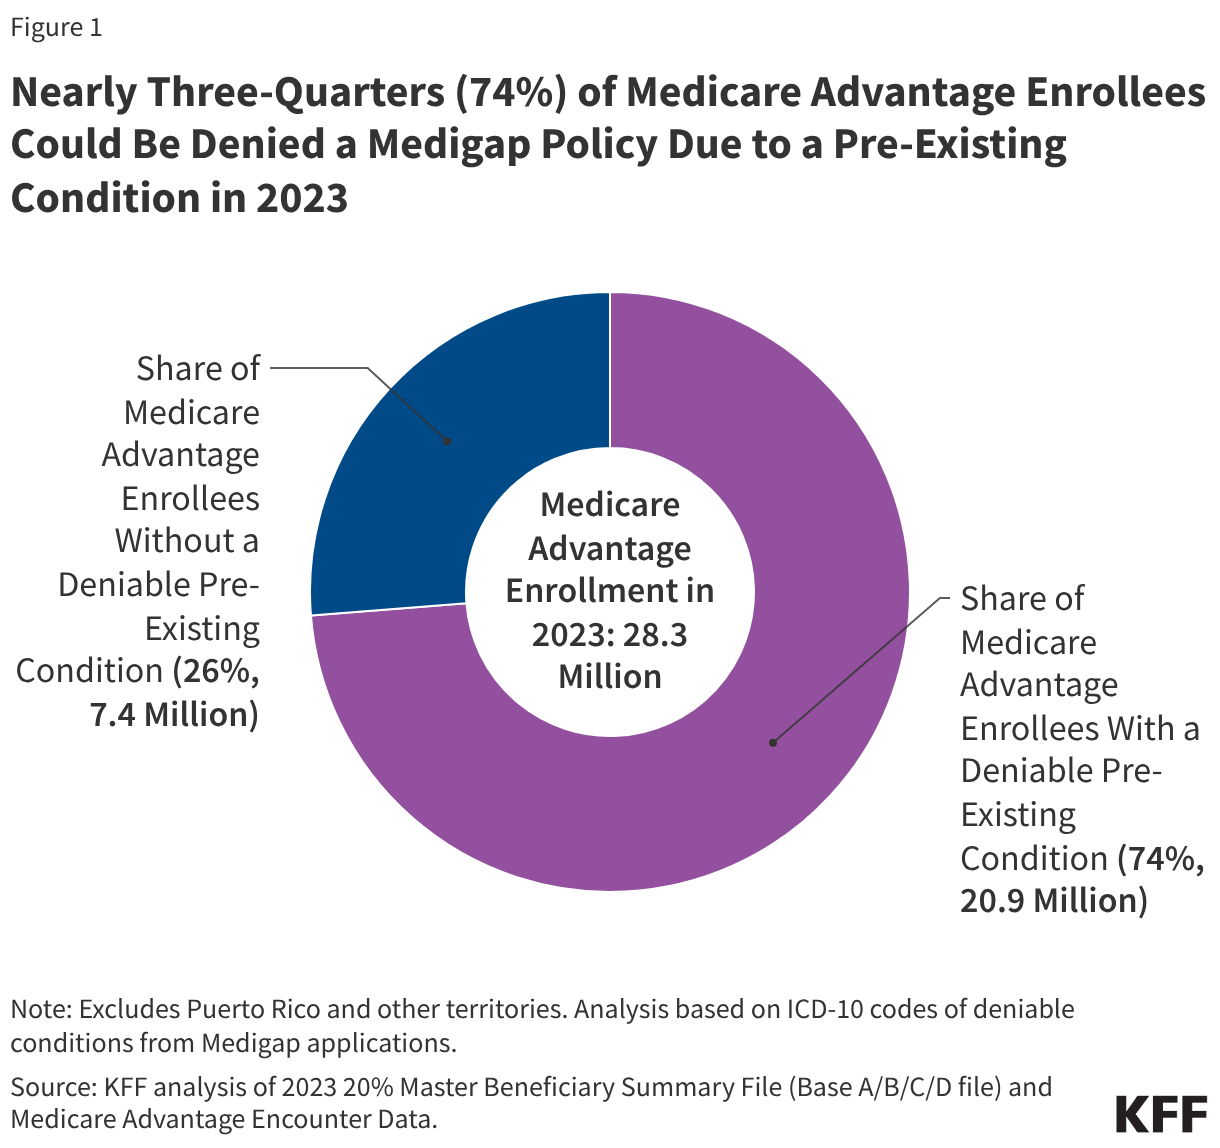
  • Nearly three-quarters of Medicare Advantage enrollees (74%) or 20.9 million people in 2023 had a pre-existing medical condition identified from KFF’s review of Medigap applications that could result in a denial for a Medigap policy.
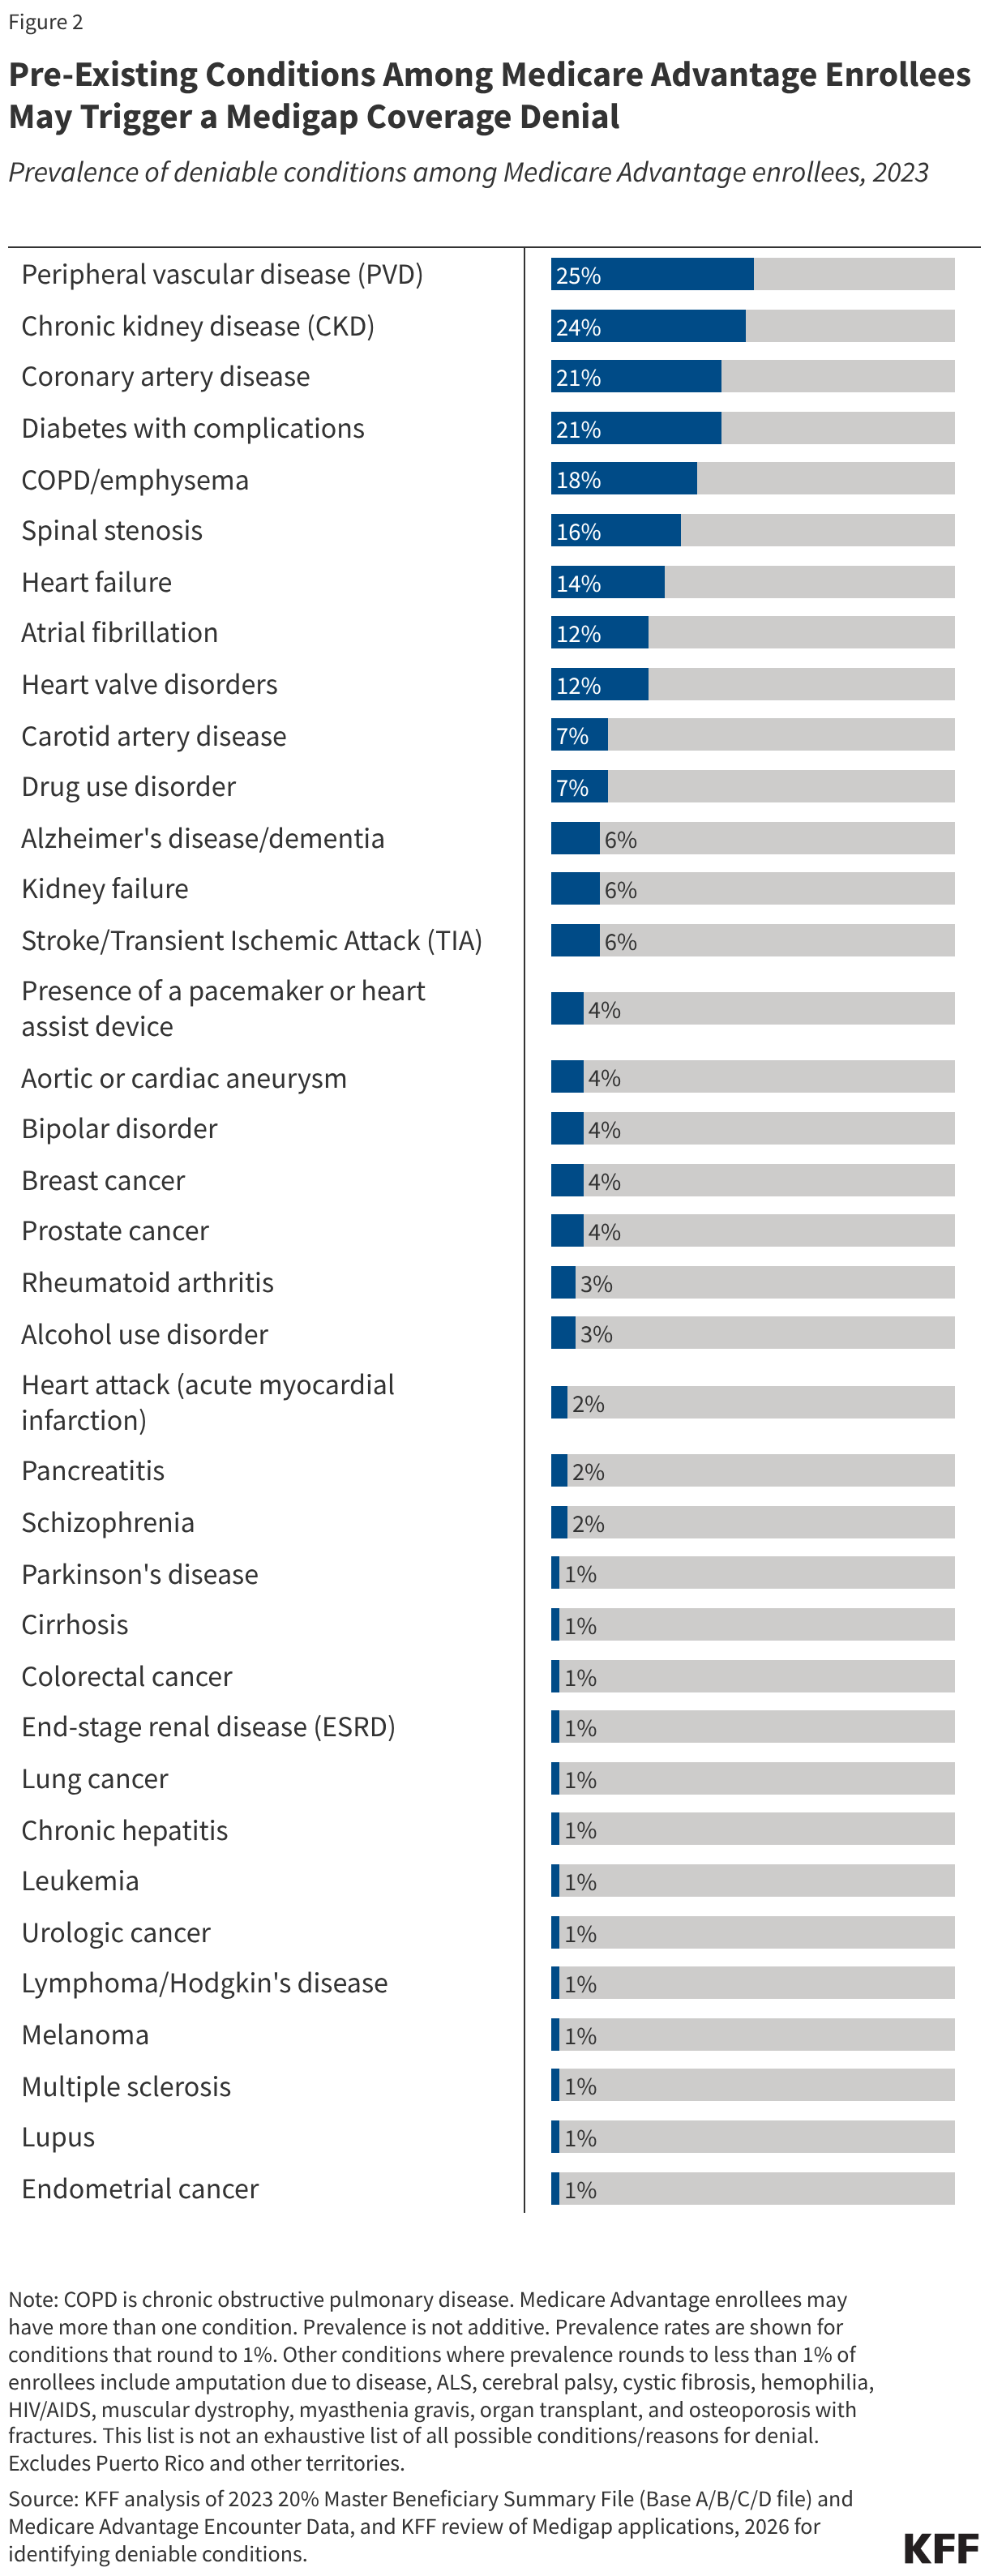
  • At least one in five Medicare Advantage enrollees have a diagnosis for peripheral vascular disease (25%), chronic kidney disease (24%), coronary artery disease (21%), or diabetes with related complications (21%) documented in the Medicare Advantage encounter data, all of which could trigger a Medigap denial.
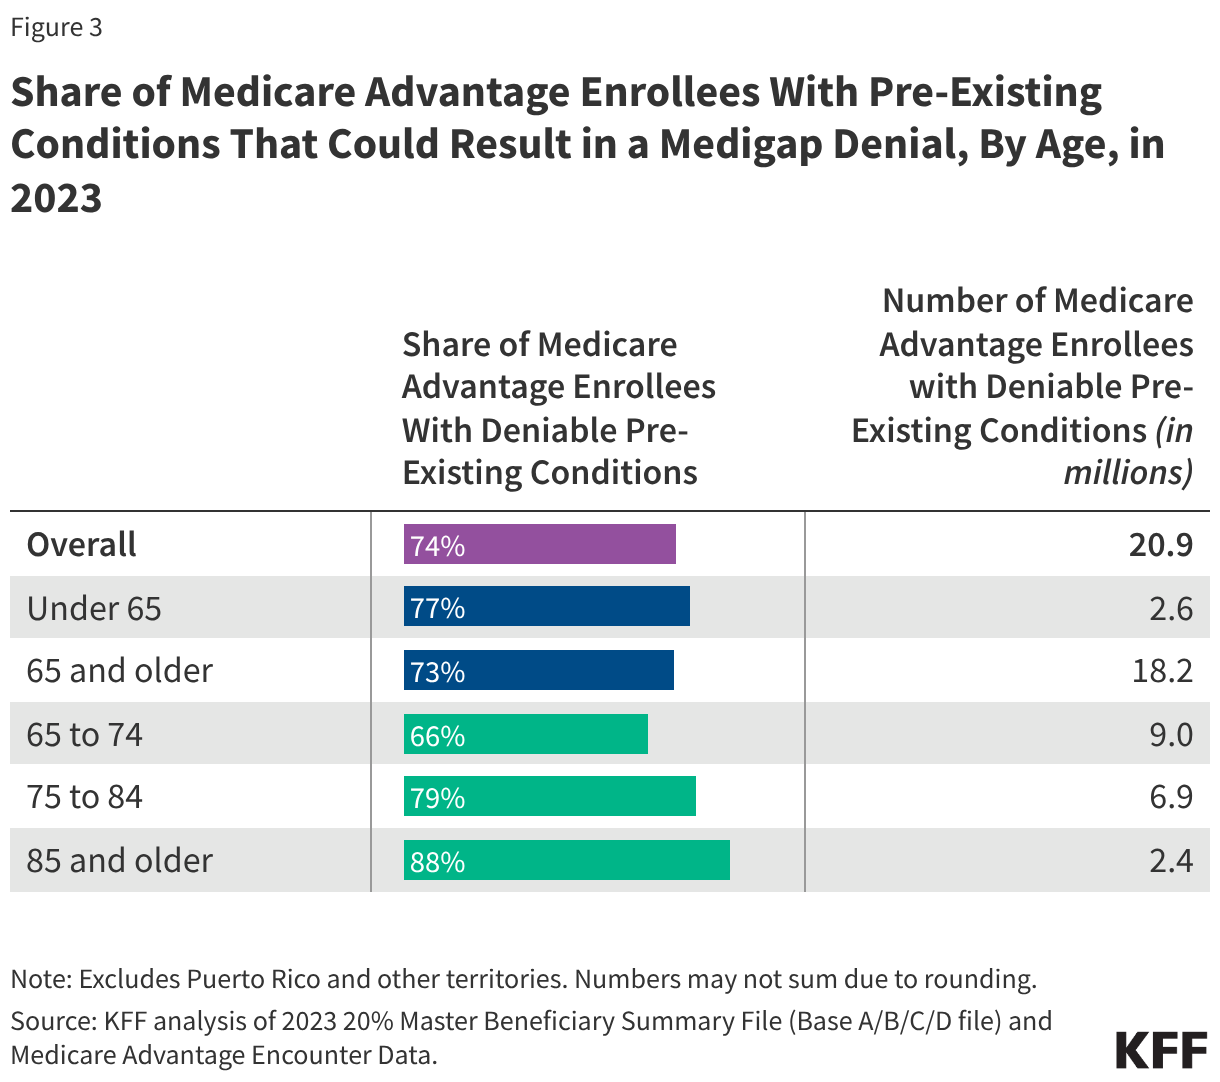
  • The share of Medicare Advantage enrollees who have a deniable pre-existing condition rises with age among people 65 and older, with close to 9 in 10 enrollees 85 and older (88%) having a medical condition that could trigger a Medigap denial.
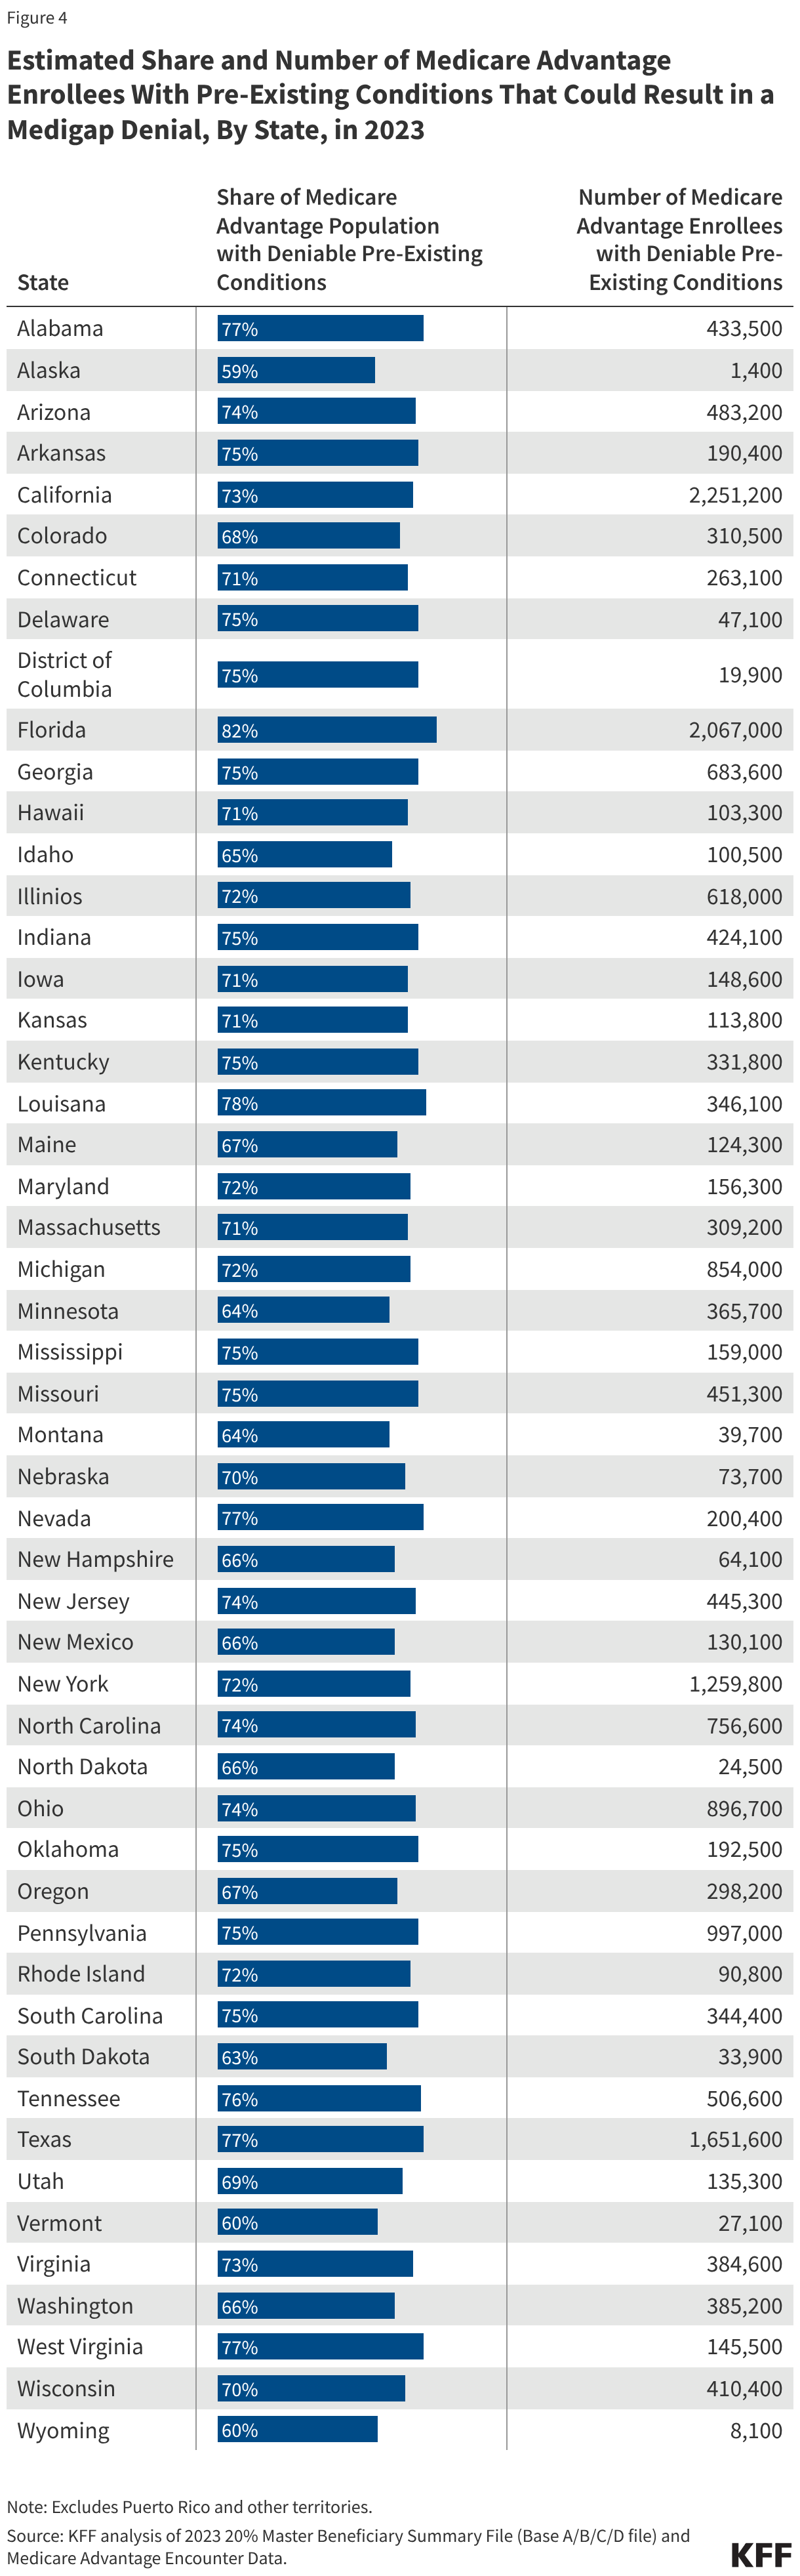
  • The share of Medicare Advantage enrollees who have a pre-existing condition that could trigger a denial for Medigap varies by state, from a high of 82% in Florida to a low of 59% in Alaska.

In 2023, 74% of Medicare Advantage enrollees had a pre-existing condition that could result in a denial for a Medigap policy.

Under federal law, insurance companies that sell Medigap policies may refuse to sell a policy to an applicant with certain medical conditions outside guaranteed issue periods. Many Medigap applications state that if an applicant answers “yes” to any health-related screening question, they are not eligible for coverage. This contrasts with other insurance products, like plans sold in the ACA Marketplace or Medicare Advantage, which are not permitted to deny coverage based on pre-existing conditions at any time.

KFF analysis of Medicare Advantage encounter data finds that nearly three-quarters (74%) of people enrolled in Medicare Advantage for the full year in 2023, or about 20.9 million people, had a condition that could trigger a denial for a Medigap policy (Figure 1). Conditions were selected if they appeared in the medical history questions on at least half of Medigap applications in KFF’s review, though this is not an exhaustive list of possible conditions or reasons that could result in a Medigap denial.

Nearly Three-Quarters (74%) of Medicare Advantage Enrollees Could Be Denied a Medigap Policy Due to a Pre-Existing Condition in 2023 (Donut Chart)

The share of Medicare Advantage enrollees who could be denied a Medigap policy may in fact be higher than 74%, because Medigap plans may deny applicants for other reasons that were not captured in this analysis but are commonly asked on Medigap applications, including recent medical service use (e.g., inpatient hospitalizations, use of home health services, or being treated in a nursing facility) or receiving medical advice, such as a recommendation to get further evaluation, diagnostic testing, treatment, or surgery for any condition, but has not yet been performed. However, some of these potential reasons for denial likely overlap with the conditions in this analysis. For example, the condition itself may have led to hospitalization or use of home health services.

Eliminating denials for pre-existing conditions would make Medigap, and by extension traditional Medicare, more accessible for people who want to switch from Medicare Advantage, but it would also increase Medigap premiums. The current one-time, six-month guaranteed issue period is intended to limit adverse selection: beneficiaries who do not buy a policy during this window risk not being able to purchase a Medigap policy later if they choose to wait until they incur health care costs. This incentivizes both healthier and sicker enrollees to join the Medigap risk pool, which holds down average premiums. Without this limit on guaranteed issue, people who initially enroll in Medicare Advantage but develop greater health needs later could more easily switch to Medicare, with its broader provider networks and less frequent use of prior authorization and purchase Medigap coverage.

Potentially deniable conditions include several chronic conditions which are prevalent in more than one in five Medicare Advantage enrollees.

At least one in five Medicare Advantage enrollees have a diagnosis for peripheral vascular disease (25%), chronic kidney disease (24%), coronary artery disease (21%), or diabetes with related complications (21%) documented in the Medicare Advantage encounter data, all of which could trigger a Medigap denial. Other deniable conditions include Alzheimer’s disease and dementia, atrial fibrillation, chronic obstructive pulmonary disease (COPD) and emphysema, carotid artery disease, cancers such as breast and prostate, heart failure, heart valve disorders, multiple sclerosis, Parkinson’s disease, spinal stenosis, stroke, among others (Figure 2). Medicare Advantage enrollees may have multiple pre-existing conditions, but one is enough to potentially trigger a Medigap denial.

Pre-Existing Conditions Among Medicare Advantage Enrollees May Trigger a Medigap Coverage Denial (Table)

Because Medicare Advantage payment relies heavily on the diagnosis codes recorded for Medicare Advantage enrollees, there is a strong financial incentive for insurers to capture as many diagnosis codes for each enrollee as possible. Coding practices in Medicare Advantage, in particular higher coding intensity, may have the effect of making more Medicare Advantage enrollees ineligible for Medigap. This is because diagnoses may be recorded for a Medicare Advantage enrollee that might not have been documented in claims if that same beneficiary had been enrolled in traditional Medicare.

The share of Medicare Advantage enrollees who have a pre-existing condition that could trigger a denial for Medigap is higher for beneficiaries under 65 than for Medicare beneficiaries 65 to 74 and rises with age among people 65 and older.

Share of Medicare Advantage Enrollees With Pre-Existing Conditions That Could Result in a Medigap Denial, By Age, in 2023 (Table)

A larger share of beneficiaries under 65 has a deniable pre-existing condition than beneficiaries age 65 to 74 (77% vs. 66%), which may be related to the fact that their eligibility for Medicare is contingent on having a long-term disabling health condition (Figure 3). Beneficiaries under 65 qualify for Medicare after receiving Social Security Disability Benefits (SSDI) for at least two years. While many disabling conditions that qualify beneficiaries for SSDI are asked about on Medigap applications, there are also other disabling conditions that do not generally appear on Medigap applications used for this analysis, including many mental health conditions and intellectual and developmental disabilities.

Because the share of beneficiaries with pre-existing conditions increases by age among those 65 and older, rising to close to 9 in 10 among those age 85 and older (88%), older Medicare Advantage enrollees may have greater difficulty obtaining a Medigap policy at a time when the need for medical services may rise, in the event that they want to switch to traditional Medicare.

The share of Medicare Advantage enrollees who have a pre-existing condition that could trigger a denial for Medigap varies by state.

On the high end, 82% of Medicare Advantage enrollees in Florida and 78% of Medicare Advantage enrollees in Louisiana have pre-existing conditions that could result in a Medigap denial. On the low end, 59% of Medicare Advantage enrollees in Alaska and 60% of Medicare Advantage enrollees in Vermont and Wyoming have a pre-existing condition that could result in denial of a Medigap policy (Figure 4).

Estimated Share and Number of Medicare Advantage Enrollees With Pre-Existing Conditions That Could Result in a Medigap Denial, By State, in 2023 (Table)

Some states provide additional guaranteed issue opportunities to purchase Medigap without regard to pre-existing conditions.

Even if Medicare Advantage enrollees have a pre-existing condition that might trigger a Medigap denial, some beneficiaries may still be able to purchase Medigap without being subject to underwriting, depending on the state where they live and other coverage they may have. For example, four states – Connecticut, Massachusetts, Maine, and New York – require insurers to offer Medigap policies on a continuous or annual basis to all beneficiaries ages 65 and older regardless of medical history. Additional considerations related to Medigap guaranteed issue opportunities are described in Box 1 and also described in detail in a separate KFF brief, Medigap Guaranteed Issue Requirements: An Overview of Federal and State Rules.

Box 1: Additional Guaranteed Issue Opportunities to Purchase Medigap

Beneficiaries with Medicaid: Medicare beneficiaries who are dual-eligible individuals, meaning they have both Medicare and Medicaid, have premium assistance, and in many cases cost-sharing protections, through Medicaid and typically do not need Medigap. However, under federal law, if dual-eligible individuals lose their Medicaid eligibility, they are not entitled to a guaranteed issue period to purchase Medigap, unless they had Medigap prior to becoming eligible for Medicaid and did not have Medicaid for more than two years. However, there are 13 states that offer guaranteed issue protections to purchase Medigap if individuals no longer qualify for Medicaid.

Beneficiaries with employer coverage: Medicare beneficiaries have a federal guaranteed issue right to purchase Medigap if their employer cancels their retiree coverage, but the federal right does not apply if their retiree benefits change or they voluntarily drop their retiree coverage. However, there are 29 states where Medicare beneficiaries have guaranteed issue protections to purchase Medigap coverage if there are some changes to their retiree coverage, such as a reduction in benefits, or if they leave their retiree plan voluntarily.

Beneficiaries under age 65: Federal law does not require Medigap insurers to sell policies to beneficiaries under 65 when they first become eligible for Medicare, and the Medicare Advantage trial period does not apply to this population. However, 38 states require insurers to issue at least one kind of Medigap policy to beneficiaries under age 65, though premiums vary across states. When people with Medicare who are under age 65 become age-eligible for Medicare at 65, they have the same time-limited federal guaranteed issue protections for Medigap as people age 65 and older, including the six-month Medigap open enrollment period, regardless of whether or not they had a Medigap policy when they were under age 65.

Methods

This analysis uses the Medicare Advantage encounter data and Master Beneficiary Summary File to identify Medicare Advantage enrollees who had a diagnosis for at least one condition that is regularly used in Medigap applications to screen out potential enrollees.

ICD-10 diagnosis codes were mapped to conditions mentioned on Medigap applications and the presence of which could result in a Medigap denial due to medical underwriting. We used the SERFF Filing Access portal to obtain Medigap applications available from the top six carriers by enrollment (UnitedHealthcare, Mutual of Omaha, Health Care Service Corporation (BCBS of Texas), CVS (Aetna), Elevance Health (Wellpoint), and Humana) based on states with the largest Medigap enrollment (CA, TX, and IL; FL has higher Medigap enrollment than IL but does not participate in SERFF). Some applications have different look-back periods of when an applicant is required to have a condition (e.g., last 2 years, last 5 years). For this analysis, we only looked for the presence of diagnoses in one year, 2023.

Conditions were selected if they appeared in the medical history questions on at least half of Medigap applications, though this is not an exhaustive list of possible conditions or reasons that could result in a Medigap denial. For example, many applications ask if an applicant has been diagnosed, treated, or had surgery for cancer. We used the CCW algorithm for common cancers (breast, prostate, colorectal, lung, endometrial, and urologic), but this is not a complete list of cancers that could result in a denial. Some applications were more explicit than others about whether having certain conditions would result in a Medigap denial and indicated that an applicant is not eligible for coverage if they answered “yes” to any health screening question. Other applications may require a medical release authorization or additional information on applicants’ health histories, including the medications they take to determine whether they qualify for coverage.

Medicare Advantage enrollees were included in the analysis if they had coverage under Medicare Parts A, B, and D and were enrolled in Medicare Advantage for all of 2023. Individuals living in territories, including Puerto Rico, were excluded. Individuals received a condition flag if a diagnosis code for one of the conditions appeared on at least one inpatient, outpatient, carrier, home health, or skilled nursing facility encounter record in 2023. Chart review records are excluded.

While this analysis is limited to Medicare Advantage enrollees, 3.5 million beneficiaries in traditional Medicare lacked supplemental coverage in 2023. Some of these beneficiaries may have missed their one-time Medigap open enrollment period or previously dropped Medigap coverage and could face denial based on pre-existing conditions if they later seek a policy. However, because the MBSF does not comprehensively identity supplemental coverage among traditional Medicare beneficiaries, we are unable to estimate how many of these 3.5 million have conditions that could result in a Medigap denial.

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

Medigap Guaranteed Issue Requirements: An Overview of Federal and State Rules

Authors: Meredith Freed, Yasmina Issaka, Nancy Ochieng, and Juliette Cubanski
Published: Oct 13, 2026

Medicare supplement insurance, known as Medigap, helps cover Medicare Part A and Part B cost-sharing requirements, including deductibles, copayments, and coinsurance. Medigap policies, which are sold by private insurance companies, are a key source of supplemental coverage for people in traditional Medicare without employer-sponsored retiree benefits or Medicaid (Medigap does not work with Medicare Advantage). In 2024, 12.9 million Medicare beneficiaries, or 46% of all traditional Medicare beneficiaries, had a Medigap policy. While there are federal and state rules that govern the issuance of Medigap policies, including around the use of medical underwriting by insurers when issuing Medigap policies, guaranteed issue protections are generally time-limited and do not extend to beneficiaries in all age cohorts equally. (For more information on the basics of Medigap, see Key Facts About Medigap Enrollment and Premiums for Medicare Beneficiaries).

This issue brief analyzes federal and state rules related to guaranteed issue requirements for Medigap policies and how they impact beneficiaries’ access to Medigap, including the implications for Medicare beneficiaries with pre-existing medical conditions and those under age 65 with long-term disabilities. This analysis is based on KFF review of federal and state insurance regulations and other publicly available information.

  • Federal law provides some guaranteed issue protections for Medicare beneficiaries who seek to purchase a Medigap policy, such as during the first six months when first enrolling in Medicare Part B, and for certain qualifying events, such as during the Medicare Advantage trial period or if a Medicare Advantage plan terminates coverage in their area.
  • Federal law allows Medigap insurers to use medical underwriting to either deny Medicare beneficiaries a policy or charge higher premiums outside of guaranteed issue periods. For example, beneficiaries may be denied a Medigap policy if they have a pre-existing condition and choose to switch from Medicare Advantage to traditional Medicare outside the initial 12-month trial period or seek to purchase a Medigap policy beyond the six-month window after enrolling in Medicare.
  • States can go beyond minimum federal requirements to establish broader guaranteed issue protections, including continuous or annual guaranteed issue requirements, establishing guaranteed issue periods for certain qualifying events, or providing guaranteed issue protections to people under age 65.
    • Eight states have relatively generous continuous or annual guaranteed issue protections.
      • Four states (CT, MA, ME, NY) require either continuous or annual guaranteed issue protections for Medigap for all beneficiaries ages 65 and older, regardless of medical history.
      • Four other states (DE, IL, MN, and RI) have expanded guaranteed issue protections, though they are not as comprehensive as in CT, MA, ME, and NY. For example, Rhode Island enacted legislation in 2025 to institute annual guaranteed issue protections for people 65 and older with Medicare Advantage to purchase a Medigap policy (though they do not apply to people with traditional Medicare who do not have a Medigap policy). And in Minnesota, there are annual guaranteed issue protections for individuals ages 65 to 70, which went into effect August 1, 2026.
    • Thirty-seven states require Medigap insurers to issue policies to Medicare beneficiaries ages 65 and older due to certain qualifying events, such as when an applicant has a change in their employer retiree coverage (29 states) or when beneficiaries lose their Medicaid eligibility (13 states).
    • Thirty-eight states require insurance companies to offer at least one kind of Medigap policy to Medicare beneficiaries under age 65 with disabilities during an initial open enrollment period, regardless of medical conditions. When these beneficiaries turn age 65, federal law entitles them to the same six-month open enrollment period for Medigap that is available to new beneficiaries ages 65 and older.

Federal Regulations Related to Medigap

Medigap insurance is subject to certain federal minimum requirements:

  • A six-month open enrollment period beginning the first month a beneficiary is enrolled in Medicare Part B, for beneficiaries ages 65 and older
  • A standardized set of benefits across Medigap policies, with 10 standard Medigap policies available to newly eligible beneficiaries. (Three states – Massachusetts, Minnesota, and Wisconsin – have a different set of standardized policies.)
  • Guaranteed plan renewability
  • Minimum medical loss ratio requirements
  • Limiting the waiting period for coverage for pre-existing medical conditions to six months for applicants that do not have at least six months of prior continuous creditable coverage
  • Prohibiting insurers from issuing new policies that cover the full Part B deductible, making Plans C and F no longer available to beneficiaries who turned age 65 on or after January 1, 2020.

During the one-time, six-month Medigap open enrollment period for beneficiaries ages 65 and older and certain other qualifying events, Medigap insurers cannot deny a Medigap policy to any qualifying applicant based on factors such as age, gender, or health status, nor can they vary premiums based on an applicant’s pre-existing medical conditions or exclude coverage for a pre-existing medical condition (i.e., medical underwriting).

The one-time, six-month guaranteed issue period is intended to mitigate potential selection issues in the Medigap market. Rather than waiting to incur high health care costs before purchasing a Medigap policy, beneficiaries must generally purchase a policy during the initial open enrollment period, or they risk not being able to purchase a Medigap policy later. This also has the effect of ensuring that the risk pool includes a mix of both healthier and sicker enrollees, which could keep premiums lower, on average.

However, as discussed in more detail below, the one-time open enrollment period also has the effect of locking people out of the Medigap market who might not be at higher risk of incurring high medical expenses in the short term. This could include, for example, a beneficiary who has been enrolled in a Medicare Advantage plan for a few years and wants to switch to traditional Medicare, but faces medical underwriting based on having pre-existing medical conditions.

Certain Circumstances Trigger Guaranteed Issue Protections

In addition to the one-time 6-month open enrollment period, there are a variety of situations that can trigger a guaranteed issue period, based on federal requirements. (States may establish additional guaranteed issue protections; see section Many States Provide Broader Guaranteed Issue Protections Than Minimum Federal Standards). In general, for qualifying events that trigger guaranteed issue rights, people ages 65 and older in Medicare generally have 63 days to apply for a Medigap policy (Table 1).

When Do People Seeking a Medigap Policy Have Guaranteed Issue Protections Under Federal Law? (Table)

Beneficiaries with Traditional Medicare and Employer Retiree Coverage: Medicare beneficiaries have federally qualified guaranteed issue rights to purchase Medigap if their employer cancels their retiree coverage. However, they do not have guaranteed issue rights to purchase Medigap if their retiree coverage changes or if they voluntarily drop retiree coverage. This includes Medicare Advantage enrollees who voluntarily leave a retiree health plan through Medicare Advantage and who seek to purchase a Medigap policy.

Beneficiaries with Traditional Medicare and Medigap: Federal law requires that a trial period applies to Medicare beneficiaries in traditional Medicare who cancel their Medigap policy when they enroll in a Medicare Advantage plan (this is not limited to just the first year of enrolling in Medicare). These beneficiaries have time-limited guaranteed issue rights to purchase their same Medigap policy if, within a year of first signing up for a Medicare Advantage plan, they decide to disenroll to return to traditional Medicare. Guaranteed issue rights also apply if their Medigap insurance company goes bankrupt or Medigap coverage ends through no fault of their own, or their Medigap insurance company commits fraud.

Beneficiaries who currently have Medigap do not have federal guaranteed issue protections to switch Medigap policies. They also do not have guaranteed issue protections if they voluntarily drop Medigap and wish to purchase a policy again later.

Beneficiaries with Medicare and Medicaid: Medicare beneficiaries who are dual-eligible individuals, meaning they have both Medicare and Medicaid, typically have coverage of premium and cost-sharing requirements from their state Medicaid program. Therefore, they do not need Medigap and in general, Medigap insurers cannot sell Medigap policies to people with Medicaid. If dual-eligible individuals lose their Medicaid eligibility, they are not entitled to a guaranteed issue period to purchase Medigap unless they had a Medigap policy prior to becoming eligible for Medicaid. In this case, a beneficiary could suspend Medigap for up to two years and would face no new medical underwriting or waiting periods for pre-existing conditions if they lose Medicaid and choose to restart their Medigap within those two years. Outside of that two-year window, medical underwriting would apply.

Beneficiaries with Medicare Advantage. Federal law requires that Medigap policies be sold with guaranteed issue rights during a specified trial period for Medicare Advantage plans. During the trial period, Medicare beneficiaries can try a Medicare Advantage plan, but if they disenroll within the first year, they have guaranteed issue rights to purchase any Medigap policy that is sold in their state. This trial period typically begins if a Medicare beneficiary joins a Medicare Advantage plan when they are first eligible for Medicare Part A at 65.

Medicare Advantage enrollees also have guaranteed issue rights to purchase a Medigap policy to supplement coverage under traditional Medicare if:

  • their Medicare Advantage plan discontinues coverage in their area
  • they move to a new area and can no longer access coverage from their Medicare Advantage plan
  • their Medicare Advantage plan is terminated
  • their Medicare Advantage plan commits fraud.

Medigap Insurers Can Deny Coverage Based on Pre-Existing Conditions, Except Under Limited Circumstances

Under federal law, insurance companies that sell Medigap policies may deny selling a policy to an applicant with certain medical conditions outside of a guaranteed issue period. This contrasts with other insurance products, like plans sold in the ACA Marketplace or Medicare Advantage, which are not permitted to deny coverage based on pre-existing conditions at any time. In most states that allow medical underwriting for Medigap, Medicare Advantage enrollees with pre-existing conditions may be reluctant to switch to traditional Medicare if they are unable to purchase a Medigap policy. This is because Medigap provides added financial protection as a supplement to traditional Medicare, which does not have an out-of-pocket spending cap for services covered under Medicare Parts A and B. In contrast, Medicare Advantage plans are required to have an out-of-pocket limit for Parts A and B.

According to KFF analysis, nearly three quarters (74%) of Medicare Advantage enrollees or 20.9 million people have a medical condition that could result in a denial for Medigap, based on 2023 data. At least one in five Medicare Advantage enrollees have a diagnosis for peripheral vascular disease (25%), chronic kidney disease (24%), coronary artery disease (21%), or diabetes with related complications (21%) documented in the Medicare Advantage encounter data, all of which could trigger a Medigap denial. Other deniable conditions include Alzheimer’s disease and dementia, atrial fibrillation, chronic obstructive pulmonary disease (COPD) and emphysema, carotid artery disease, cancers such as breast and prostate, heart failure, heart valve disorders, multiple sclerosis, Parkinson’s disease, spinal stenosis, stroke, among others. Further, Medigap plans may deny applicants for other reasons that are not related to having a specific condition including recent medical service use (e.g., inpatient hospitalizations, use of home health services, or being treated in a nursing facility) or receiving medical advice, such as a recommendation to get further evaluation, diagnostic testing, treatment or surgery for any condition, but has not yet been performed.

Access to Medigap Is More Limited for Medicare Beneficiaries Under Age 65 with Disabilities

Under federal law, Medigap insurers are not required to sell Medigap policies to the just under 7 million Medicare beneficiaries who are under age 65, a majority of whom qualify for Medicare based on having a long-term disability and receiving Social Security disability benefits (a small number qualify due to having ESRD or ALS). Higher rates of Medicaid coverage among these beneficiaries, who tend to have relatively low incomes, also contribute to low enrollment in Medigap among beneficiaries under age 65. For these reasons, a significantly smaller share of traditional Medicare beneficiaries under age 65 have Medigap compared to beneficiaries with traditional Medicare ages 65 and older: 8% vs. 50% in 2024 (Figure 1).

A Small Share (8%) of Adults Under 65 in Traditional Medicare Had a Medigap Policy in 2024 (Stacked Bars)

However, when these beneficiaries turn 65 and become age-eligible for Medicare, the six-month Medigap open enrollment period becomes available. While there are no federal guaranteed issue protections in place for beneficiaries under age 65, many states have rules in place that require insurance companies to offer at least one kind of Medigap policy to Medicare beneficiaries under age 65 with disabilities during an initial open enrollment period, regardless of medical conditions, as described below.

Many States Provide Broader Guaranteed Issue Protections Than Minimum Federal Standards

Eight States Have Relatively Generous Guaranteed Issue Protections on an Either Continuous or Annual Basis

Four states – Connecticut, Massachusetts, Maine, and New York – require Medigap insurers to offer policies either continuously throughout the year or once per year to Medicare beneficiaries ages 65 and older without regard to their medical conditions (Figure 2; Appendix Table 1). Another four states -- Delaware, Illinois, Minnesota, and Rhode Island -- have relatively comprehensive expanded consumer protections that provide additional Medigap guaranteed issue periods for Medicare beneficiaries.

Eight States Have Relatively Generous Guaranteed Issue Protections on an Either Continuous or Annual Basis (Choropleth map)

Connecticut and New York have continuous open enrollment, with guaranteed issue rights throughout the year. Massachusetts regulation requires an annual guaranteed issue open enrollment period from February 1 to March 31, but all insurers in Massachusetts offer continuous open enrollment throughout the year. Maine requires insurers to issue Medigap Plan A during an annual one-month open enrollment period of the insurer’s choosing. Plan A is less comprehensive than some Medigap plans, such as Plan G – the most popular policy in 2025.

In 2025, Rhode Island enacted legislation that provides an annual guaranteed issue period for Medicare Advantage enrollees 65 and older to purchase a Medigap plan (though this protection does not apply to people with traditional Medicare who do not have a Medigap policy). This annual guaranteed issue period is during the Medicare open enrollment period from October 15 to December 7.

In 2025, Delaware enacted legislation that provides two annual guaranteed issue periods for Medicare Advantage enrollees 65 and older to purchase a Medigap plan (though this protection does not apply to people with traditional Medicare who do not have a Medigap policy). These periods are during the Medicare open enrollment period and during the Medicare Advantage open enrollment period (January 1 to March 31). While insurers cannot deny any Medigap application, they may charge higher premiums based on medical underwriting and impose a 6-month waiting period to cover costs related to pre-existing conditions.

Minnesota enacted legislation that includes the institution of a guaranteed issue open enrollment period for individuals age 65 to 70. The opportunity to purchase a Medigap policy falls during the annual Medicare open enrollment period and can only be used one time. The law also permits insurers to charge individuals 15% more in premiums than the standard community rate beginning in 2026, with premiums increasing annually by 5%, until 2030 and subsequent years, when the premium penalty is 35%. These premiums are in effect for the duration of the policy. These new rules went into effect August 1, 2026, and represent a scaled-back version of previous legislation that would have established broader guaranteed-issue rights in the state, which passed but was not implemented.

In Illinois, one insurer – Blue Cross Blue Shield of Illinois – offers policies to anyone 65 and older who seeks to purchase a Medigap plan on a guaranteed issue basis through the year, though this is not a statutory requirement and is potentially subject to change.

States establish certain rules for Medigap insurers, including how to set premiums, and premiums may be based on factors such as a policyholder’s age, smoking status, gender, residential area, and rating system, even during open enrollment and guaranteed issue periods. Due to the variety of factors at play, KFF analysis shows that there is not a clear relationship between states with continuous or annual guaranteed issue protections and having consistently higher premiums for Medigap than in other states. However, three of the states with more robust guaranteed issue protections (New York, Connecticut, and Maine) do have the highest average premiums for Plan G. Further, Minnesota commissioned a study on the impact of instituting annual guaranteed issue protections and estimated that average annual premiums across all Minnesota Medigap plans would be 6% higher during the first year of implementation, with enrollment in Medigap expected to be 32% higher without these changes in effect.

Thirty-Seven States Require Medigap Insurers to Issue Medigap Policies to Beneficiaries Ages 65 and Older Due to Certain Qualifying Events

Thirty-seven states (including Delaware, Illinois, Maine, Minnesota, Rhode Island since they do not have continuous guaranteed issue protections) require Medigap insurers to offer policies to eligible applicants ages 65 and older based on certain qualifying events beyond the minimum federal standards (Figure 3, Appendix Table 1):

  • Twenty-nine states require Medigap insurers to issue policies when an applicant has a change in their employer retiree coverage, such as a reduction in benefits or an increase in costs, depending on the state. Some states also provide guaranteed protections for individuals who choose to voluntarily leave their retiree health plan. This qualifying event is more expansive than federal law, which applies only when retiree coverage is completely eliminated by the employer.
  • Thirteen states require Medigap insurers to issue policies if Medicare beneficiaries lose their Medicaid eligibility. Medicare beneficiaries who are dually-eligible individuals would no longer have premium and cost-sharing protections through Medicaid if they lose their Medicaid coverage.
  • Nineteen states offer the Medicare Advantage trial period to beneficiaries older than 65. Typically, the Medicare Advantage trial period applies only when people enroll in Medicare Advantage when they are first eligible for Part A at 65. However, 12 states tie eligibility for the trial period to Part B enrollment, meaning those who delay Part B enrollment, because they are still working for example, could still be eligible for the Medicare Advantage trial period, even if they are older than 65 when they enroll in Part B. An additional state (Wisconsin) has a specific regulation that requires the trial period to be available to those who recently left employer coverage and enroll in a Medicare Advantage plan for the first time. The remaining six states still tie eligibility for the trial period to when someone first enrolls in Part A, but enrollees can be older than 65.
  • Six states have guaranteed issues rules for other types of qualifying events. For example, Maine extends the federally-required Medicare Advantage trial period from one year to three years. California allows Medicare Advantage enrollees to purchase a Medigap policy from the same Medicare Advantage insurer they are enrolled in (if it sells one) if their Medicare Advantage plan reduced any of its benefits, increased cost sharing, or terminated a contract with a provider currently treating them. In Maryland, there is a new guaranteed issue period for individuals who became eligible for Medicare before January 1, 2020, and have a qualifying federal Special Enrollment Period. These individuals would typically only be able to purchase Plans F or C following a qualifying event, but this new guaranteed issue period would allow them to purchase Plans G or D.
Thirty-Seven States Require Medigap Insurers to Issue Medigap Policies to Beneficiaries Ages 65 and Older to Due to Certain Qualifying Events (Choropleth map)

Twenty of these states provide guaranteed issue protections for current Medigap policyholders who want to switch policies (Figure 3, Appendix Table 1):

  • Sixteen states have what are called “birthday rules” (CA, DE, ID, IL, IN, KY, LA, MD, NV, NM, OK, OR, UT, VA, WV, WY), which require Medigap insurers to allow current policyholders to switch each year to a different Medigap policy with equal or lesser benefits from either the same or different insurance carrier, depending on the state, around the time of their birthday. Depending on the state, these Medigap policyholders have between 30 and 63 days to switch policies. (This allowance does not enable beneficiaries who do not already have Medigap to newly purchase a Medigap policy).
  • Rhode Island requires Medigap insurers to allow current Medigap policyholders to switch to any Medigap policy made available by any insurer during the Medicare open enrollment period.
  • Missouri requires Medigap insurers to allow current Medigap policyholders to switch to an equivalent policy from a different insurer within 30 days before or after the annual anniversary date of their policy.
  • Maine requires Medigap insurers to allow current Medigap policyholders to switch to a policy with equal or less generous benefits at any time during the year if there is less than a 90-day gap in coverage.
  • Washington requires Medigap insurers to allow Medigap policyholders to switch to a policy with equal or less generous benefits at any time during the year if there is less than a 90-day gap in coverage, though policyholders with Medigap Plan A are limited to switching to another Plan A, while those with Plans B through N can switch to any other Plan B through N.

Thirty-Eight States Require Medigap Insurers to Offer an Initial Guaranteed Issue Period to Purchase Medigap to People Under Age 65 with Disabilities

Thirty-eight states require insurers to issue at least one kind of Medigap policy to beneficiaries under age 65, typically through an initial open enrollment period (Figure 4, Appendix Table 2). Of these 38 states, 27 require insurers to sell all plan types to people under age 65 during the guaranteed issue period. The remaining 12 states and DC do not require insurers to sell a Medigap policy to people under age 65 with disabilities, including people with ESRD and ALS.

Thirty-Eight States Require Medigap Insurers to Offer at Least One Policy to Beneficiaries Under Age 65 With Disabilities During an Initial Open Enrollment Period (Choropleth map)

Requirements for People with ESRD and ALS:

Of the 38 states that require insurers to issue at least one kind of Medigap policy to people under age 65 with disabilities, 28 states explicitly require insurers to also sell these policies to people with ESRD and 25 states specify they must be sold to people with ALS. Four states (CA, MA, VT, and NE) explicitly state that insurers are not required to sell policies to people with ESRD, and the remaining six states are silent on whether insurers must sell at least one policy to people with ESRD. Thirteen states (including CA, MA, and VT) are silent on whether insurers must sell policies to people with ALS.

The same four states that have expanded Medigap guaranteed issue rights most broadly for beneficiaries ages 65 and older also require broader access to Medigap for people under age 65.

In addition to offering an initial guaranteed issue period to purchase Medigap, Massachusetts, Maine, New York, and Connecticut require continuous or annual guaranteed protections for people under age 65 with disabilities, though with slightly different requirements than for people ages 65 and older: in Massachusetts, insurers are not required to issue policies to people with ESRD, while in Connecticut, insurers must issue Plan A to people under age 65, as well as Plans B, C, and/or D for insurers that sell these plan types to people ages 65 and older. In Maine, all Medigap plan types must be available to beneficiaries under age 65 with disabilities during the open enrollment period, but after this period, insurers are only required to issue Medigap Plan A to beneficiaries under age 65 during the one-month open enrollment period that happens each year (the same as for people ages 65 and older).

Another three states provide more expansive Medigap guaranteed issue protections for people under age 65.

In Rhode Island, in addition to an initial enrollment period for people under 65 to purchase plan A, Medicare Advantage enrollees under age 65 are afforded an annual guaranteed issue period to purchase plan A. In Delaware, in addition to an initial enrollment period for people under 65 to purchase Medigap, Medicare Advantage enrollees under 65 who try to enroll in Medigap outside this period cannot be denied a Medigap plan, though insurers may charge higher premiums based on medical underwriting and a 6-month waiting period to cover services related to pre-existing conditions is permitted. In both states, these protections do not apply to people under 65 who are in traditional Medicare and outside their initial enrollment period. In Illinois, in addition to an initial enrollment period for people under 65 to purchase Medigap, beneficiaries under 65 can purchase a Medigap plan from Blue Cross Blue Shield annually from October 15 to December 7.

19 of the 38 States That Require Medigap Insurers to Offer Policies to Eligible Applicants Under Age 65 During an Initial Open Enrollment Period Also Do So for Certain Qualifying Events

Nineteen states require Medigap insurers to offer policies to eligible applicants under age 65 based on certain qualifying events (Figure 5, Appendix Table 3):

  • Ten states require Medigap insurers to issue policies when an applicant under age 65 has a change in their employer retiree coverage – the same states that also offer guaranteed issue rights for applicants ages 65 and older who have a change in their employer (retiree) coverage. However, some states have more restrictive policies for people under age 65. For example, in Texas, this guaranteed issue right applies only for Medigap Plan A for people under age 65 with ESRD or ALS (this right does not apply to those under 65 with other disabilities).
  • Eight states require insurers to issue Medigap policies to beneficiaries under age 65 who lose their Medicaid eligibility. These eight states also offer the same guaranteed issue protections for people ages 65 and older, but in the case of Texas, the guaranteed issue right for people under age 65 applies only in the case of Plan A for people under age 65 with ESRD or ALS (this right does not apply to those under 65 with other disabilities).
  • Eleven states provide guaranteed issue protections for current Medigap policyholders who want to switch policies, including seven states that require Medigap insurers to allow Medigap policyholders under age 65 to switch to a policy with equal or less generous benefits (e.g., under “birthday rules”).
  • Some states have other types of qualifying events for beneficiaries under age 65:
    • Illinois extends the same federal Medicare Advantage guaranteed issue protections that are available to people ages 65 and older, to people under age 65 in the state. For example, Medicare Advantage enrollees under age 65 in Illinois who move out of their Medicare Advantage plan’s service area, or whose Medicare Advantage plan goes out business, have a 6-month guaranteed issue right to purchase a Medigap policy.
    • Oregon requires that insurers offer a guaranteed issue period to individuals who move to Oregon from a state that does not require Medigap insurers to issue policies to people under age 65.
Nineteen States Require Medigap Insurers to Offer Policies to Eligible Applicants Under Age 65 With Disabilities During Additional Qualifying Events (Choropleth map)

The state-level analyses on guaranteed issue protections for people ages 65 and older and people under age 65 with disabilities are based on a review of each state’s regulations, guidance documents/manuals, directives, and other publicly accessible government-issued documents.

Additionally, KFF staff contacted states’ insurance departments or State Health Insurance State Health Insurance Department Program (SHIP) offices for clarity in cases where publicly accessible documents were silent on a particular issue. 

For the state-level analysis for people ages 65 and older:

  • States are marked as “no” if their regulations or other publicly accessible documents do not specify any additional qualifying events (beyond the federal standard).

For the state-level analysis for people under age 65:

  • States are marked as “no” to having any special qualifying events if 1) they do not require insurers to offer Medigap policies to people under age 65, or 2) they do not have any specified qualifying events or guaranteed issued protections for people under age 65, based on KFF review of state regulations, guidance documents, and contact with insurance departments or State Health Insurance Department Program (SHIP).
  • States are marked as “not specified” if publicly accessible documents do not specify requirements pertaining to each guaranteed issue qualifying event. These qualifying events were identified based on whether they are available to people 65 and older in that state.

Although best efforts were made to check each state’s regulations, guidance documents, and call insurance departments/SHIP offices, it is possible that states marked as “not specified” have rules that were not identified by the research team.

Medigap Guaranteed Issue Requirements for Medicare Beneficiaries Ages 65 and Older by State, 2026 (Table)
States with Initial Open Enrollment Period for Medigap for Medicare Beneficiaries Under Age 65 by State, 2026 (Table)
Medigap Guaranteed Issue Requirements for Medicare Beneficiaries Under Age 65 by State, 2026 (Table)

Key Facts About Medigap Enrollment and Premiums for Medicare Beneficiaries

Published: Oct 13, 2026

Medicare currently provides health insurance coverage to more than 70 million people in the U.S. However, people with Medicare can face substantial cost-sharing requirements for Medicare-covered services, and unlike most other types of health insurance, coverage under traditional Medicare provides no cap on out-of-pocket spending. While more than half of Medicare beneficiaries are currently enrolled in Medicare Advantage plans, which are required to have an out-of-pocket cap, 28.2 million beneficiaries are enrolled in traditional Medicare and lack this same automatic protection. Many Medicare beneficiaries have modest incomes and little savings to draw on if they incur substantial medical expenses.

To fill this gap in coverage under traditional Medicare, the Medicare supplement insurance market, also known as Medigap, plays a key role in enhancing the affordability of medical care for beneficiaries in traditional Medicare by helping policyholders pay their Medicare cost-sharing requirements and by limiting their exposure to catastrophic out-of-pocket medical costs.

This brief presents facts about Medigap, including the characteristics of Medicare beneficiaries with a Medigap policy, variation in Medigap enrollment by state, and Medigap premiums. This analysis is based on data from the National Association of Insurance Commissioners (NAIC) compiled by Mark Farrah Associates (MFA), through the end of 2025 (the most recent year of annual data) and the Centers for Medicare & Medicaid Services (CMS) Medicare Current Beneficiary Survey 2024 Survey File data. See methods for more information. A companion brief: Medigap Guaranteed Issue Requirements: An Overview of Federal and State Rules analyzes federal and state guaranteed issue rules and how they impact beneficiaries’ access to Medigap and another brief, Nearly Three-Quarters of Medicare Advantage Enrollees Could be Denied a Medigap Policy Due to a Pre-Existing Condition, analyzes the share of Medicare Advantage enrollees who could be denied a Medigap policy due to having a pre-existing condition.

  • In 2024, 12.9 million, or just under half (46%) of people in traditional Medicare had a Medigap policy. Compared to all traditional Medicare beneficiaries in 2024, traditional Medicare beneficiaries with a Medigap policy are more likely to be White, have higher incomes, report better health and be 65 and older. Among traditional Medicare beneficiaries, a smaller share of beneficiaries under age 65 with disabilities have a Medigap policy compared to beneficiaries ages 65 and older (8% vs 50%), due in part to a lack of Medigap guaranteed issue protections under federal law for those under age 65.
  • The share of traditional Medicare beneficiaries with Medigap varies by state, ranging from 14% in Hawaii to 75% in Iowa.
  • Of the 10 standardized Medigap policy types, Medigap Plan G, which is the most comprehensive Medigap policy available to newly eligible Medicare beneficiaries, was the most popular plan type in 2025, accounting for 46% of all policyholders, or 6.3 million people. Part F, which has the same benefits as Plan G but also covers the Part B deductible, has the second largest share of Medigap policyholders in 2025 (30% or 4.2 million people), but it has not been available to newly eligible beneficiaries since 2020.
  • The average monthly premium among current Medigap policyholders was $244 in 2025, or $2,926 for a full year of coverage.
  • Medigap premiums vary by state and by policy type. For example, in 2025, the average monthly premium for people enrolled in Plan G was $194 ($2,323 for 12 months), but this varied from $164 in New Mexico to $257 in New York.
  • On average, Medigap premiums among current policyholders increased 7% between 2024 and 2025, and 20% over the five years between 2020 and 2025. These increases translated to an additional $192 annually between 2024 and 2025, and $492 more in total between 2000 and 2025. But the increase for Plan G was higher – 13% more on average between 2024 and 2025 and a 38% increase between 2020 and 2025.

Medicare beneficiaries can choose to get their Medicare Part A and B benefits through the traditional Medicare program or a Medicare Advantage plan. Medicare Advantage plans are private plans that cover Medicare Part A and B benefits and typically also the Part D prescription drug benefit. Among the nearly 62 million people enrolled in Medicare Part A and B in 2024, slightly less than half (45%, or 27.8 million) of Medicare beneficiaries were in traditional Medicare. Most traditional Medicare beneficiaries have some form of additional coverage that helps to cover Medicare’s cost-sharing requirements, such as Medigap, employer-sponsored retiree benefits, or Medicaid, but 2.9 million beneficiaries lack any source of additional coverage. 

Medigap is private supplemental health insurance that helps people with traditional Medicare cover Medicare Part A and Part B cost-sharing requirements, including deductibles, copayments, and coinsurance. (Medigap does not work with Medicare Advantage.) Medigap is the primary source of supplemental insurance for people in traditional Medicare without employer-sponsored retiree benefits or Medicaid. In 2024, 12.9 million Medicare beneficiaries, or 46% of all traditional Medicare beneficiaries, had a Medigap policy.

By helping to cover Medicare’s cost-sharing requirements, Medigap insurance limits the financial exposure of Medicare beneficiaries and provides protection against catastrophic expenses for Medicare-covered services. There are different types of Medigap policies that provide different levels of cost-sharing assistance (see Appendix Table 3). Medigap policies also make health care costs more predictable by spreading costs over the course of the year through monthly premium payments and reduce the paperwork burden for beneficiaries associated with medical bills.

Characteristics of People with Medigap

A larger share of traditional Medicare beneficiaries with Medigap than traditional Medicare beneficiaries overall are White (92% vs 83%), have incomes of $40,000 or above (68% vs 61%), report their health as excellent, very good, or good (88% vs 82%), and are ages 65 and older (99% vs 91%) (Figure 1; See Appendix Table 1 for a comparison of characteristics of Medigap enrollee to beneficiaries with other types of coverage).

Medigap Policyholders Are More Likely to Be White, Have Higher Income, and Report Better Health Status Compared to Traditional Medicare Beneficiaries Overall (Stacked Bars)

Federal law offers a one-time, six-month Medigap open enrollment period for beneficiaries ages 65 and older when they age onto Medicare. However, this guaranteed issue right does not extend to Medicare beneficiaries under age 65 who qualify for Medicare on the basis of having a long-term disability. Because Medicare beneficiaries under age 65 may have difficulty purchasing a Medigap policy, a much smaller share of traditional Medicare beneficiaries under age 65 and older have a Medigap policy compared with people age 65 and older (6% versus 47%).

Most states (38 states) go beyond federal law and require Medigap insurers to offer at least one policy to people under age 65 during an initial open enrollment period, but premiums in these states vary and may be higher for people under age 65 (see section below Premium Rules Vary Across States That Require Insurers to Offer at Least One Medigap Policy Type to People Under Age 65 for more details).

Additionally, Medigap premiums can be costly (as discussed in more detail in the section below Premiums Vary Across Medigap Policies), making it more difficult for people with lower incomes to afford a Medigap policy. This, along with higher rates of supplemental coverage under Medicaid, could be a factor in lower rates of enrollment of Black and Hispanic Medicare beneficiaries in traditional Medicare plus Medigap compared to Medicare Advantage (see Appendix Table 1), since Black and Hispanic beneficiaries have lower income and assets compared to White beneficiaries. Black and Hispanic beneficiaries are also more likely to report relatively poor health and have higher prevalence rates of certain chronic conditions that would be classified as pre-existing conditions by Medigap insurers, which could also make it difficult for individuals in these groups to obtain Medigap, particularly outside of guaranteed issue periods when medical underwriting is not allowed.

Medigap Enrollment Varies by State

Medigap enrollment varies widely by state: from 14% of traditional Medicare beneficiaries in Hawaii to 75% in Iowa, based on KFF analysis of 2025 NAIC data (Figure 2, Appendix Table 1). In eleven states, 60% or more of Medicare beneficiaries with coverage of both Part A and B under traditional Medicare have a Medigap policy.

Medigap Enrollment Varies by State (Choropleth map)

Medigap Provides Varying Levels of Coverage of Medicare Cost Sharing Depending on the Policy Type

There are 10 different types of Medigap policies (labeled A through N), each having a different, standardized set of benefits (Appendix Table 3).

Plan G is the most popular Medigap policy, accounting for 46% of all policyholders, or 6.3 million people, in 2025 (Figure 3). Plan G is the most comprehensive policy available to newly eligible Medicare beneficiaries, covering the Part A deductible and all cost sharing for Part A and B covered services, but not the Part B deductible. Plan G has become the most popular plan since a change in law that prohibited Medigap policies from covering the Part B deductible for newly eligible beneficiaries, which meant that Plan C and Plan F could no longer be sold to new beneficiaries who turned 65 on or after January 1, 2020. Plan F has the second largest share of Medigap enrollment, covering 36% of Medigap policyholders or 4.2 million people. Plan N has the third largest share of Medigap enrollment, covering 10% of policyholders or 1.5 million people. Plan N is similar to Plan G, except that there are Part B copayments for some office visits and some emergency room visits, and it does not cover Part B excess charges.

Plan G is the Most Popular Policy Type in the Medigap Market in 2025, With 46% of Medigap Enrollees, or 6.3 Million People, Choosing that Policy (Table)

Buying a Medigap Policy is Generally Limited to Specified Time Periods and Circumstances

Federal Medigap Rules

Federal law provides guaranteed issue protections for Medigap policies during a one-time, six-month Medigap open enrollment period for beneficiaries ages 65 and older, which begins the first month of Medicare Part B coverage, as well as for certain qualifying events. Some of these qualifying events may include instances when people involuntarily lose certain types of supplemental coverage, such as when an employer cancels retiree coverage or when a Medicare Advantage plan discontinues coverage in their area. The federally guaranteed one-time, six-month Medigap open enrollment period does not extend to beneficiaries with long-term disabilities who qualify for Medicare before age 65.

Beneficiaries also have guaranteed issue rights during specified “trial” periods, such as the first year that people who are first eligible for Medicare Part A at 65 are enrolled in Medicare Advantage. During that time, beneficiaries can try a Medicare Advantage plan, and if they disenroll within the first year, they have guaranteed issue rights to purchase any Medigap policy that is sold in their state.

During these defined periods, Medigap insurers cannot deny a policy based on age, gender, or health status, vary premiums based on pre-existing conditions, or exclude coverage for pre-existing conditions. However, under federal law, Medigap insurers may impose a waiting period of up to six months to cover costs related to pre-existing conditions if the applicant did not have at least six months of prior continuous creditable coverage. For qualifying events that trigger guaranteed issue rights, people ages 65 and older in Medicare generally have 63 days to apply for a Medigap policy.

State-Level Medigap Rules

States can choose to establish Medigap rules that provide a greater level of consumer protection than the federal standards. Eight states have relatively generous continuous or annual guaranteed issue protections. Four states – Connecticut, Massachusetts, Maine, and New York – require Medigap insurers to offer policies either continuously throughout the year or once per year to Medicare beneficiaries age 65 and older without regard to their medical conditions. This guaranteed issue right extends to those who have been in traditional Medicare past their initial enrollment period and those in Medicare Advantage whose enrollment may have extended beyond the initial 12-month “trial right” period.

In addition, Rhode Island and Delaware enacted legislation in 2025 to institute annual guaranteed issue protections for people with Medicare Advantage to purchase a Medigap policy (though they do not apply to people with traditional Medicare who do not have a Medigap policy). In Delaware, while insurers cannot deny any Medigap application, they may charge higher premiums based on medical underwriting and impose a 6-month waiting period to cover services related to pre-existing conditions. Effective August 2026, Minnesota also began offering annual guaranteed issue protections for Medicare beneficiaries ages 65 to 70. Illinois insurer Blue Cross Blue Shield of Illinois also offers policies to anyone 65 and older who seeks to purchase a Medicare supplement on a guaranteed issue basis through the year, though this is not a statutory requirement and is potentially subject to change.

Other states have also expanded on the federal minimum standards to allow beneficiaries to purchase Medigap on a guaranteed issue basis after certain qualifying events or for beneficiaries under 65 with disabilities to purchase Medigap during an initial open enrollment period. (For more information on qualifying events and additional state-level Medigap protections, see Medigap Guaranteed Issue Requirements: An Overview of Federal and State Rules for more details.)

Premiums Vary Across Medigap Policies

Although Medicare is a federal program, Medigap policies are insurance products that are regulated at the state level, meaning states establish certain rules for Medigap insurers, including how to set premiums. Premiums may be based on factors such as a policyholder’s age, smoking status, gender, and residential area, even during open enrollment and guaranteed issue periods.

There are three different rating systems that can affect how Medigap insurers determine premiums: community rating, issue-age rating, or attained-age rating.

  • Community rating: The same premium is generally charged to everyone, regardless of age or gender. Premiums may go up because of inflation and other factors, such as smoking status and residential area, but not due to age.
  • Issue-age rating: The premium is based on the age of the beneficiary when they purchase the Medigap policy. Premiums are lower for people who buy at a younger age and higher for those who buy at older ages. Premiums may increase over time due to inflation and other factors, such as smoking status and residential area, but not due to age.
  • Attained-age rating: The premium is based on a beneficiary’s current age, so the premium goes up as they get older. Premiums are lower for younger buyers but increase as they get older, which means that premiums may be the least expensive at first but can eventually become the most expensive. Premiums may also increase due to inflation and other factors, such as smoking status and residential area.

States can impose regulations on which of these rating systems are permitted or required for Medigap policies sold in their state. Currently, most states (37 states and D.C.) allow any rating system. Nine states (AR, CT, ID, MA, ME, MN, NY, VT, and WA) require premiums to be community rated among policyholders ages 65 and older, while another four states (AZ, FL, GA, and MO) permit issue-age rating but prohibit attained-age rating (Appendix Table 4). Depending on state rules, insurers may apply a mix of rating systems for the Medigap policies they offer and policyholders can choose which rating type applies to the policy they buy, though insurers may choose to not offer plans for all rating types. For example, those seeking to purchase Medigap may have fewer options for community rated plans in states that permit any rating type.

Premium Rules Vary Across States That Require Insurers to Offer at Least One Medigap Policy Type to People Under Age 65

There are 38 states that require insurers to make at least one kind of Medigap policy guaranteed issue during an initial open enrollment period for beneficiaries under age 65, which is not a federal requirement. In these states, rules vary as to whether the same premiums are required for people under ages 65 and people ages 65 and older.

Among these 38 states, 25 states limit how much insurers can charge in premiums for beneficiaries under age 65. (Figure 4, Appendix Table 5). The remaining 13 states have no specified rules on premium costs.

In the 38 States Requiring Insurers to Offer at Least One Medigap Plan to Beneficiaries Under Age 65 With Disabilities, Rules on Premiums Vary by State (Table)

Average Medigap Premiums Vary Among Current Policyholders by State and Policy Type

The average monthly Medigap premium across all current Medigap policyholders (including people under 65, people who smoke tobacco, and people who are in a high deductible or SELECT plan) was $244, ranging from $214 in Hawaii to $306 in New York in 2025 (Figure 5, Appendix Table 4).

The Average Monthly Medigap Premium Across All Current Medigap Policyholders Was 4 and Varied Across States, Ranging From 4 in Hawaii to 6 in New York (Choropleth map)

Average premiums also vary considerably depending on the policy type. For Plan G, the most popular and comprehensive plan available to newly eligible beneficiaries, the average monthly premium among current policyholders in 2025 was $194, and ranged from $164 in New Mexico to $257 in New York (Figure 6, Appendix Table 4). For Plan F, the plan with the second highest enrollment (but no longer available to Medicare beneficiaries who turned 65 after as of January 1, 2020), the average premium among current policyholders is $325, ranging from $243 in Vermont to $378 in Nebraska. The difference in premiums may be due in part to the fact that Plan F covers the Part B deductible, which Plan G does not cover, and that Plan G is enrolling new and younger beneficiaries, while Plan F covers an older group of beneficiaries since new enrollees are not eligible, creating different risk pools, though it may also be related to other factors, as described below. These data reflect what people currently pay, some of whom have had a Medigap plan for many years, rather than what a new enrollee might pay.

The Average Monthly Medigap Premium Among Current Policyholders Varies by Policy Type - the Average Premium for Plan G Was 4, Ranging from 4 to 7 (Bar Chart)

In the five states with the most expensive monthly premiums on average in 2025 for Plan G, four states (NY, CT, ME, WA) require community rating, while the fifth (FL) only allows issue-age rating. Further, the three states with highest premiums (NY, CT, and ME) have continuous or annual guaranteed issue protections. For Plan F, the state with the highest monthly premium is Nebraska, which is not community rated, followed closely by New York, which is community rated. The three states with the next highest premiums for Plan F (IN, IL, and ND) are not community rated and do not have guaranteed issue protections.

Overall, for average Medigap premiums across all current policyholders, there is no clear relationship between states with community rating rules or guaranteed issue protections and premium levels. For example, among guaranteed issue states, New York has the highest average monthly premium, but average monthly premiums in Connecticut and Maine are only slightly above the national average and the average in Massachusetts is slightly below the national average.

Differences in average premiums across states can be due to several factors, including Medigap rating requirements, guaranteed issue requirements, the number of Medicare beneficiaries, the characteristics of the Medicare population, Medicare Advantage penetration, urbanicity of the counties, and health care cost and usage patterns. Due to data limitations, differences in average Medigap premiums by gender, age, or smoking status cannot be evaluated.

Premium costs are one of the primary concerns for people with Medigap. KFF focus groups indicate that while most beneficiaries with Medigap are satisfied with their coverage and like many of its elements, including coverage of most or all of Medicare’s cost-sharing requirements, comprehensiveness of their coverage, control over their health care, and ability to see any provider they want (by virtue of being in traditional Medicare rather than Medicare Advantage), some participants noted their premiums were expensive or cost more than they would like.

Average Medigap Premiums Have Increased Over Time and Vary by Plan Type

From 2024 to 2025, the average monthly Medigap premium increased by 7%, from $228 to $244, while the monthly Part B premium increased by 6% (from $174.70 to $185) – both outpacing the 2.7% increase in inflation. From 2020 to 2025, monthly Medigap premiums among current Medigap policyholders across all plan types increased 20% on average, increasing from $203 in 2020 to $244 in 2025 (Figure 7). Over the same time frame, the average monthly premium for Medicare Part B increased by 28% (from $144.60 to $185) and the consumer price index (CPI-U) increased by 24%.

The Average Monthly Medigap Premium Across All Current Medigap Policyholders Increased by 7% from 2024 to 2025 and by 20% from 2020 to 2025 (Column Chart)

The increase in Medigap premiums also varies by plan type. For example, from 2024 to 2025, average Plan G premiums increased by 13% from $171 to $194 and average Plan F premiums increased by 8% from $300 to $325. From 2020 (when Plans D and G became first available) to 2025, overall average Medigap premiums increased by 20%, but for Plan G specifically, the average premium among current Medigap policyholders increased by 38% from $140 to $194 (Figure 8). Similarly, for Plan F, average premiums increased by 37% over that time frame from $238 to $325 (Figure 8). The only Medigap policy that experienced a decrease in the average monthly premium between 2020 and 2025 is Plan M, with less than 0.1% of Medigap enrollment, which decreased by 20% (from $242 to $193)—although consistent with all other Medigap policy types, the average premium for Plan M increased between 2024 and 2025.

Medigap Premiums Increased by Nearly 40% For Plans F and G from 2020 to 2025 (Grouped column chart)

Average Medigap premiums may have increased at different rates across plan types and time periods due to several factors, such as Medigap rating requirements, guaranteed issue requirements, the characteristics of the Medicare population, Medicare Advantage penetration in an area, and health care cost and usage patterns. In addition, because in many states it is difficult to switch Medigap plans (unless the state has a “birthday rule” or other opportunities to switch plans), some enrollees may face escalating Medigap premiums but are unable to purchase a cheaper policy. This may be particularly true for policyholders of Plans C or F, which are not open to newly eligible Medicare beneficiaries and cover the Part B deductible, which made these policies more expensive relative to Plans D and G, respectively.

“New or Innovative” Benefits in Medigap Policies

According to federal guidelines that took effect in the early 2000s, Medigap insurers may offer policies that cover “new or innovative” benefits that are cost-effective, in addition to the standardized Medigap benefits for cost-sharing assistance provided in a given policy. These new or innovative benefits can include vision, dental, and hearing benefits, access to a 24/7 nurse phone line, access to Silver Sneaker fitness benefits, and other wellness benefits – benefits that are not covered under traditional Medicare. Medigap policies that include these types of additional benefits often have slightly higher premiums than the standard version of the policy. There is no publicly available enrollment data on these policies specifically.

These benefits can vary across policy types and insurers. For example, some policies can include coverage of specific dental services, such as 100% coverage of dental diagnostic evaluations, preventive services, and diagnostic radiographs (x-rays), 75% of extractions and 50% of some restorative services (i.e. fillings) from in-network dentists, though they may not cover more comprehensive dental services. For other policies, rather than dental insurance, enrollees can receive discounts off nationally contracted rates for a range of dental services that are not covered by traditional Medicare, including cleanings, exams, fillings and crowns, from in-network dentists.

These additional benefits may be offered to help Medigap insurers compete for business with Medicare Advantage plans, nearly all of which offer coverage of dental, vision, and hearing services, as well as other extra benefits. KFF focus groups show that the availability of extra benefits in Medicare Advantage plans, such as dental and vision, is a major consideration when beneficiaries make their Medicare coverage choices. Moreover, KFF’s analysis of television ads from 2022 finds that messaging about extra benefits was mentioned in more than 90% of ads promoting Medicare Advantage. Dental coverage was the most advertised extra benefit (included in 84% of ads), followed by coverage of vision (63%) and hearing (56%) services.

Characteristics of People With a Medigap Policy and Other Types of Medicare Coverage (Table)
Number and Share of Medicare Beneficiaries with a Medigap Policy in 2025 (Table)
Standard Medigap Plan Benefits, 2026 (Table)
Average Medigap Premiums by State and Plan Type, 2025 (Table)
Premium Rules for States with Initial Open Enrollment Period for Medigap for Medicare Beneficiaries Under Age 65, 2026 (Table)

This analysis uses data from Health Coverage PortalTM, a market database maintained by Mark Farrah Associates, which includes information from the National Association of Insurance Commissioners (NAIC). We used the “Medicare Supplement Market Data” report from 2020-2025 for this analysis. For the analysis of Medigap enrollment and premiums, territories, including Puerto Rico, are excluded. For Medigap enrollment overall, data reported to the Department of Managed Health Care in California (554,225 beneficiaries in 2025) is included in overall California enrollment counts, but this data is not included for analysis of enrollment by policy type. For the analysis of average premiums among current Medigap policyholders, only data that is reported to the NAIC is included because data from the California Department of Managed Health Care does not include information about premiums or policy type. For that analysis, KFF excluded policies that have negative or zero dollars in premiums. Premiums for current policyholders include those who smoke tobacco and those with high deductible or SELECT policies.

For characteristics of Medicare beneficiaries with Medigap versus those with Medicare Advantage, KFF used the Centers for Medicare & Medicaid Services (CMS) Medicare Current Beneficiary Survey 2024 Survey File data. Data excludes beneficiaries with Part A only or Part B only for most of the year or Medicare as a Secondary Payer. Persons of Hispanic origin may be of any race but are categorized as Hispanic; other groups are non-Hispanic.

Global COVID-19 Tracker

Published: Oct 13, 2026

Editorial Note: The Policy Actions tracker will no longer be updated as the data source has ceased tracking government responses to COVID-19. For more information, please visit the Oxford Covid-19 Government Response Tracker.

This tracker provides the cumulative number of confirmed COVID-19 cases and deaths, as well as the rate of daily COVID-19 cases and deaths by country, income, region, and globally. It will be updated weekly, as new data are released. As of March 7, 2023, all data on COVID-19 cases and deaths are drawn from the World Health Organization’s (WHO) Coronavirus (COVID-19) Dashboard. Prior to March 7, 2023, this tracker relied on data provided by the Johns Hopkins University (JHU) Coronavirus Resource Center’s COVID-19 Map, which ended on March 10, 2023. Please see the Methods tab for more detailed information on data sources and notes. To prevent slow load times, the tracker only contains data from the last 200 days. However, the full data set can be downloaded from our GitHub page. While the tracker provides the most recent data available, there is a two-week lag in the data reporting.

Note: The data in this tool were corrected on March 18, 2024, to clarify that they represent new cases and deaths over a full week rather than the average per day over a seven-day period.

This tracker contains information on policy measures currently in place to address the COVID-19 pandemic. Policy categories currently being tracked include social distancing & closure measures, economic measures, and health systems measures. Policies are tracked at the country-, income-, and region-level. Please see the Methods tab for more detailed information on data sources and notes.

Social Distancing and Closure Measures

As countries continue to implement policies to prevent the transmission of SARS-CoV-2, the virus that causes COVID-19, these tables and charts show which social distancing and closure measures are currently in place by country.

Global COVID-19 Policy Actions

Economic Measures

The COVID-19 pandemic has placed an unprecedented strain on country economies. These tables and charts show which economic-related measures, namely income support and debt relief, are currently in place by country.

Global COVID-19 Policy Actions

Health Systems Measures

The COVID-19 pandemic continues to strain and disrupt global health systems. These tables and charts show which health systems measures are currently in place by country.

Global COVID-19 Policy Actions

Cases and Deaths

SOURCES

As of March 7, 2023, all data on COVID-19 cases and deaths are drawn from the World Health Organization’s (WHO) Coronavirus (COVID-19) Dashboard. Prior to March 7, 2023, this tracker relied on data provided by the Johns Hopkins University (JHU) Coronavirus Resource Center’s COVID-19 Map, which ends on March 10, 2023. Population data are obtained from the United Nations World Population Prospects using 2021 total population estimates. Income-level classifications are obtained from the latest World Bank Country and Lending Groups. Regional classifications are obtained from the World Health Organization.

Policy Actions

NOTES

Policy actions data include the measure that was in place for each indicator at the country-level as of the end of 2022. Policy actions data will no longer be updated as the data source has ceased tracking government responses to COVID-19. For more information, please visit the Oxford Covid-19 Government Response Tracker.

Social Distancing and Closure Measures

Under 'Stay At Home Requirements', exceptions for leaving the house may include anything from being able to leave for daily exercise, grocery shopping, and essential trips, to only being allowed to leave once a week, or one person may leave at a time, etc. Under 'Workplace Closing', partial closing includes instances in which a country recommends closing the workplace (or working from home); businesses are open but with significant COVID-19-related operational adjustments; or when workplaces require closing for only some, but not all, sectors or categories of workers. Under 'School Closing', partial closing includes instances in which a country has recommended school closures; all schools are open but with significant COVID-19-related operational adjustments; or some schools, but not all, are closed; full closing includes schools that are in session but operating virtually. Under 'Restrictions On Gatherings', partial restrictions include restrictions on gatherings of more than 10 people; full restrictions include restrictions on gatherings of 10 people or less. Under 'International Travel Controls', partial restrictions include screening and quarantine requirements for those entering the country. Values for ‘Cancel Public Events’ were not recodified.

Economic Measures

Under 'Income Support', narrow support includes instances in which a country's government is replacing less than 50% of lost salary (or if a flat sum, it is less than 50% median salary); broad support includes instances in which a country's government is replacing 50% or more of lost salary (or if a flat sum, it is greater than 50% median salary). Under 'Debt/Contract Relief', narrow support includes instances in which a country's government is providing narrow relief, such as relief specific to one kind of contract.

Health Systems Measures

Under 'Vaccine Eligibility', partial availability includes availability for some or all of the following groups: key workers, non-elderly clinically vulnerable groups, and elderly groups, or for select broad groups/ages. Under 'Facial Coverings', recommend/partial requirement includes instances in which a country's government recommends wearing facial coverings, requires facial coverings in some situations, and requires facial coverings when social distancing is not possible. 

SOURCES

Data on and descriptions of government measures related to COVID-19 provided by the Oxford Covid-19 Government Response Tracker (OxCGRT). For more detailed information on their data collection and methodology, please see their codebook and interpretation guide.

The Business of Health with Chip Kahn

AI in Health Care: Who Gets Left Behind?

October 12, 2026

Video

Audio

About this Episode


Episode 19, AI Series: Health care’s AI future is being built right now. The open question is “for whom?” Dr. Uché Blackstock — emergency physician, former associate professor at NYU School of Medicine, founder and CEO of Advancing Health Equity, and author of The New York Times bestseller “Legacy: A Black Physician Reckons with Racism in Medicine” — joins host Chip Kahn to argue that AI governance should be shaped not only by regulators and review boards, but by the communities the tools are meant to serve. Dr. Blackstock explains why she is skeptical of technology that presents itself as neutral, how average performance can conceal unequal harm, and what equitable AI design would require. She also makes the business case for equity and describes trust as infrastructure that can be designed into the system. Will the AI revolution reach the patients American health care has historically failed — or pass them by?

The Host


Headshot photo of Chip Kahn wearing a navy blue suit with a red tie, red pendant on lapel, and glasses.

Sr. Visiting Fellow

Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.

Guest


Founder and Chief Executive Officer, Advancing Health Equity

Dr. Uché Blackstock is founder and CEO of Advancing Health Equity, a strategic consulting firm that partners with leaders and organizations across health care and public health to build more equitable, accountable systems where everyone can thrive. She is an emergency physician, health equity strategist, and author of the New York Times bestseller Legacy: A Black Physician Reckons with Racism in Medicine.

Prior to founding Advancing Health Equity, Dr. Blackstock served as an associate professor in the Department of Emergency Medicine at NYU Langone Health and as faculty director of recruitment, retention, and inclusion in NYU Langone Health’s Office of Diversity Affairs.

Recognized by TIME on its inaugural TIME100 Health list in 2024, and by Forbes and Fortune for her leadership, Dr. Blackstock helps organizations move from intention to measurable change.


SERIES

This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.

The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.

HHS’s Elimination of Disparate Impact to Determine Discrimination: Potential Implications for Health and Health Care

Authors: Latoya Hill, Jameson Floyd, and Samantha Artiga
Published: Oct 9, 2026

Introduction

On July 23, 2026, the Department of Health and Human Services (HHS) finalized revisions to regulations implementing Title VI of the Civil Rights Act of 1964 to eliminate disparate impact as a basis for determining whether discrimination has occurred in programs, services, or activities receiving HHS federal financial assistance. It was issued following Executive Order 14281, “Restoring Equality of Opportunity and Meritocracy,” and similar actions by other federal agencies, including the Department of Justice (DOJ), Department of Education (DOE), and Department of Housing and Urban Development (HUD). This issue brief provides background on Title VI, summarizes the key changes in the 2026 final rule, and discusses the potential implications for racial and ethnic health disparities.

The rule marks a significant change in the federal government’s approach to enforcing civil rights protections, which may have significant implications for its enforcement of civil rights law and health and health care disparities. The changes under the rule narrow the scope for administrative enforcement of civil rights law; may allow for policies and practices that lead to disparate outcomes in health and health care to remain in place, which may exacerbate disparities; and may reduce proactive review of whether policies and practices have unintended disproportionate effects on certain racial or ethnic or other protected groups.

Overview of the HHS Title VI Civil Rights Rule

Title VI of the Civil Rights Act of 1964 is a federal law that prohibits discrimination based on race, color, or national origin in programs and activities receiving federal financial assistance. It was enacted during the Civil Rights Movement in response to widespread racial discrimination by institutions receiving federal funds, including hospitals that refused to treat Black patients, maintained segregated wards and waiting rooms, or otherwise provided unequal care. Title VI has since served as a cornerstone of federal civil rights enforcement across health care, education, and other federally funded programs.

While the Supreme Court has interpreted Title VI to prohibit intentional discrimination, federal agencies historically implemented broader protections against discrimination through regulations. In its initial regulations implementing Title VI, HHS (then the Department of Health, Education and Welfare) and other federal agencies also prohibited disparate-impact discrimination. Disparate impact refers to policies or practices that have a disproportionately adverse effect on people of a particular race, color, or national origin, even when there is no evidence of intentional discrimination. These regulations recognized that facially neutral policies can perpetuate or exacerbate inequities in access to programs, services, and benefits.

In health care, disparate impact can arise from inequities embedded in institutional policies and practices, although intentional discrimination still persists. For example, historical discriminatory policies, such as redlining, have lasting effects today, leading to residential segregation of Black and Hispanic people into urban neighborhoods with more limited resources and increased health risks. Within medicine, disproven beliefs about biological differences by race persist today and have led to race permeating clinical decision making and treatment in multiple ways, including through its use in clinical algorithms, tools, and treatment guidelines. Similarly, language barriers can reduce the quality of care patients receive and increase the risk of adverse outcomes or medical errors. Studies have found that inadequate language assistance can delay patients’ access to timely care and contribute to suboptimal care and dissatisfaction with the care received, leading to poor chronic disease management and resulting in worse health outcomes. 

The federal government has used disparate-impact regulations for over 50 years to investigate and resolve policies and procedures of recipients of federal financial assistance that disproportionately negatively affect a protected group. For example:

  • HHS’s Office for Civil Rights (OCR) investigated the proposed closure of University of Pittsburgh Medical Center (UPMC) Braddock, a hospital serving a predominantly Black community in Pennsylvania, to assess whether the closure would have a disparate impact on Black residents’ access to care. The investigation resulted in a voluntary resolution agreement requiring UPMC to implement measures to reduce potential barriers to care, including expanded transportation services, enhanced primary care and behavioral health services, and ongoing monitoring of the closure’s impact on the affected community.
  • Similarly, OCR entered into a voluntary resolution agreement with Mee Memorial Hospital (MMH) following an investigation into allegations that the hospital had failed to provide meaningful language assistance to Triqui-speaking patients with limited English proficiency (LEP). Although the hospital was not intentionally withholding services from Mexican indigenous patients, it’s lack of language assistance disproportionately prevented them from receiving effective care. The agreement required the hospital to strengthen its language access policies, interpreter services, staff training, and monitoring.
  • More recently,in 2021, HHS’s OCR and the DOJ investigated the Alabama Department of Public Health (ADPH) over concerns that its wastewater and public health practices disproportionately burdened Black residents of Lowndes County. The agencies reached an interim resolution agreement requiring ADPH to take steps to address the community’s longstanding exposure to raw sewage, including improving access to functioning septic systems, suspending criminal enforcement against residents unable to afford compliant systems, and strengthening public health data collection and infrastructure planning. In 2024, HHS and DOJ reported progress in implementing these reforms. However, in April 2025, the Trump Administration terminated the agreement, ending the federal agencies’ enforcement of the reforms.

Disparate-impact standards have also shaped HHS guidance to recipients about designing and administering programs and policies. For example, HHS issued guidance on serving individuals with LEP explaining that recipients could violate Title VI by using criteria or methods that had the effect of discriminating based on national origin and translated this standard into expectations for providing meaningful access to care. HHS’s Office of Minority Health (OMH) National Culturally and Linguistically Appropriate Services (CLAS) Standards also reflect principles underlying disparate-impact protections, particularly in their language access standards. During the COVID-19 pandemic, HHS’s OCR issued guidance advising that Title VI applied to procedures, criteria, and methods of administration that have a disparate impact based on race, color or national origin. The guidance specifically identified examples of disparate-impact discrimination that could arise in COVID-19 vaccination programs, such as requirements for vaccines to be distributed solely through pharmacies or appointments needing to be scheduled online, which could disproportionately limit access in communities of color, even in the absence of discriminatory intent. HHS also advised vaccine providers to review policies for barriers, collect and analyze demographic data, address language and transportation barriers, and locate vaccination sites in historically underserved communities. HHS also incorporated disparate-impact principles into a training curriculum for medical students by including examples of facially neutral health care policies that could disproportionately limit access for racial and ethnic communities and instructing participants to consider whether less discriminatory alternatives could achieve the same objectives.

Potential Implications of Eliminating Disparate Impact Enforcement

The 2026 final rule eliminates disparate impact as a basis for administratively enforcing Title VI under HHS’s implementing regulations. Under the revised regulations, HHS will enforce Title VI only when there is evidence of intentional discrimination based on race, color, or national origin. As a result, a policy or practice that disproportionately affects a protected group, by itself, is no longer sufficient to establish a violation of Title VI under HHS regulations. HHS states that these revisions are intended to align its regulations with the text of Title VI, Supreme Court precedent, and Executive Order 14281, “Restoring Equality of Opportunity and Meritocracy,” issued by President Trump on April 23, 2025, directing federal agencies to eliminate the use of disparate-impact liability. The final rule also clarifies that statistical evidence showing racial or ethnic disparities may still be considered as part of an investigation, but disparities alone are not sufficient to establish discrimination absent evidence of intentional discriminatory treatment.

The 2026 final rule marks a shift in HHS’s approach to investigating and resolving Title VI complaints and will likely have a range of implications for enforcement of civil rights law and health disparities. The changes under the rule:

  • Narrow the scope for administrative enforcement of civil rights law. The rule changes what the federal government will identify as discrimination in its activities and investigations since the federal government will no longer enforce policies and procedures that result in disparate effects for protected groups but cannot be tied to intentional discrimination. Moreover, parties seeking administrative enforcement of the law will face a higher burden to demonstrate discrimination, since they must be able to show intentional discrimination.
  • May allow for policies and practices that lead to disparate outcomes in health and health care to remain in place, which may exacerbate disparities. As noted, even in the absence of intentional discrimination, policies and procedures may lead to disparate impact for protected groups. For example, hospital or clinic closures; reductions in obstetric, behavioral health, or specialty services; provider network changes; transportation or service relocation decisions; eligibility or enrollment procedures; lack of effective language access services; and resource allocation decisions may lead to or exacerbate disparities because of longstanding differences in where individuals live and the resources they have available, where health care services are located, insurance coverage, transportation, and other social and economic factors. Moreover, the increasing use of artificial intelligence (AI) in health care and language services may exacerbate cases of disparate impact because underlying data, model design, or implementation may reinforce or widen existing disparities.
  • Reduce incentives for HHS and recipients of federal financial assistance to ensure policies and practices are equitable and do not disproportionately adversely affect certain racial or ethnic groups or other protected groups. Without disparate impact as an enforcement standard, the federal government has reduced incentive to investigate policies and procedures for discrimination unless there are claims of intentional discrimination. Despite civil rights statutes remaining in full effect, federal funding recipients may have less incentive to proactively assess the equity implications of institutional decisions, policies, and procedures. Some organizations may continue to focus on equitable practices as a part of their accreditation standards, state laws, Medicaid requirements, quality improvement initiatives, or organizational priorities, but they will not be subject to federal enforcement to ensure equitable impacts or outcomes for the groups they serve unless there is evidence of intentional discrimination.

In the absence of Title VI disparate impact enforcement, other federal and state authorities may provide mechanisms for addressing disparate impacts, but these protections may have more limited reach and may apply to different protected groups, entities, programs, jurisdictions, or forms of discrimination than Title VI. For example, Section 1557 of the Affordable Care Act continues to prohibit discrimination in covered health programs based on race, color, national origin, disability, age and sex and includes requirements related to providing meaningful language access. However, the Administration has indicated it will make changes to Section 1557 implementing regulations. Medicaid also provides mechanisms for addressing disparities, particularly through managed care contracting practices, although efforts vary across states. States may also retain or establish their own protections against disparate-impact discrimination. For example, California statute prohibits discrimination in state-funded programs and activities based on a broader range of protected characteristics than Title VI with state regulations prohibiting practices with discriminatory effects, providing a state-level disparate impact standard similar to one the one eliminated from HHS’s Title VI regulations. Illinois also enacted the Civil Rights Safeguard Act in 2026, expanding existing state protections against disparate impact discrimination in employment, financial credit, and public accommodations, including health care.  However, without a federal standard of enforcement, protections and mechanisms to address discrimination will vary across states.

How Much Do People with Medicare Pay for Coverage?

Published: Oct 9, 2026

The Medicare program provides health insurance coverage to over 70 million people ages 65 or older and younger adults with long-term disabilities. While Medicare covers a wide range of health care services, Medicare beneficiaries generally pay out-of-pocket for their monthly premiums, deductibles, and cost sharing for Medicare covered services. Medicare premiums and other cost-sharing requirements have increased steadily in recent years and are projected to continue growing over the next decade. At the same time, many Medicare beneficiaries have modest incomes which can make it difficult to afford these costs: one in four Medicare beneficiaries lived on incomes below $24,600 per person in 2024, and out-of-pocket spending on Medicare premiums and cost-sharing expenses accounted for more than a third (36%) of the average Medicare beneficiary’s Social Security income in 2023.

Out-of-pocket costs may also vary depending on the choices Medicare beneficiaries make about their coverage. People with Medicare can choose to receive their benefits through traditional Medicare or through a privately administered Medicare Advantage plan. Beneficiaries in traditional Medicare can sign up for prescription drug coverage through a stand-alone Part D plan, and may also purchase a Medicare supplemental insurance policy, known as Medigap, to assist with Medicare cost sharing. Medicare Advantage plans typically include prescription drug coverage, as well as limits on how much enrollees pay out of pocket each year for Medicare covered services (in contrast to traditional Medicare, which has no limit on out-of-pocket costs), but most plans also require enrollees to use a specified network of providers or charge higher cost sharing for services from out-of-network providers. Each of these Medicare coverage options comes with different premium and cost-sharing requirements, as well as considerable variation from plan to plan. Overall, navigating these options and expenses can be complex, and the costs can be substantial, particularly for beneficiaries with high health care needs.

This brief provides an overview of the costs faced by Medicare beneficiaries in traditional Medicare, Medicare Advantage, and Medicare Part D, including premiums, deductibles, copays, and coinsurance, focusing on costs in 2026. (The brief will be updated with cost information for 2027 when available.)

Premiums for Medicare Part A and Part B

Part A Premium: $0 per month for most Medicare beneficiaries

Part B Premium: $202.90 per month (standard); income-related adjustments apply for people with higher incomes

Part A Premiums

Most Medicare beneficiaries, whether they are covered under traditional Medicare or Medicare Advantage, pay no monthly premium for Medicare Part A, which covers inpatient hospital stays, short-term nursing facility care, hospice, and some home health services. People generally qualify for premium-free Part A if they or a spouse have worked at least 40 quarters (10 years) in jobs where they paid Medicare payroll taxes. People who are otherwise eligible for Medicare but do not meet this requirement may still enroll in Part A but are required to pay a monthly premium. In 2026, the Part A premium is $311 per month (or $3,732 for the year) for beneficiaries with more than 30 quarters but less than 40 quarters of covered employment and $565 per month (or $6,780 for the year) for beneficiaries with fewer than 30 quarters of covered employment.

Late enrollment penalty. If a Medicare-eligible person is required to pay a Part A premium but delays enrollment beyond their initial enrollment period and lacks qualifying group coverage in the interim, they are subject to a late enrollment penalty in the form of a 10% increase to their monthly Part A premium when they enroll in Part A. The Part A late enrollment penalty applies for twice the number of years enrollment was delayed. For example, if a person with 30 quarters of covered employment was initially eligible to enroll in Part A in January 2023, but delayed enrollment for two years until January 2025, they would incur late enrollment penalties until 2029 and would pay $342.10 per month for Part A coverage in 2026 (based on $311 times 10%).

Part B Premiums

Beneficiaries are required to pay a monthly premium for Part B coverage, whether they are covered under traditional Medicare or Medicare Advantage. Part B covers physician visits, outpatient hospital services, preventive services, diagnostic tests, and physician-administered drugs. In 2026, the standard Part B premium is $202.90 per month (or $2,434.80 for the year). Beneficiaries with incomes greater than $109,000 for individuals or $218,000 for married couples in 2026 pay a higher, income-adjusted Part B premium ranging from $284.10 to $689.90 per person per month in 2026 (Figure 1). Beneficiaries with low incomes and modest assets may qualify for help from their state Medicaid program to pay their Medicare Part B premium.
Medicare Beneficiaries with Incomes Above 9,000 Per Person Pay an Income-Related Monthly Adjustment to the Standard Part B Premium (Table)

Late enrollment penalty. As with Part A, Medicare-eligible people who delay enrolling in Part B beyond their initial enrollment period and who lack other qualifying group coverage in the interim are subject to a late enrollment penalty when they enroll in Part B. The Part B late enrollment penalty is a lifetime penalty and is calculated as 10% of the monthly standard Part B premium for each 12-month period enrollment was delayed. For example, someone who delayed enrollment in Part B for two years would face a 20% monthly Part B premium penalty and would pay $243.48 per month in 2026 (based on $202.90 times 20%).

Cost-Sharing Requirements in Traditional Medicare

Part A:

  • Deductible: $1,736 per inpatient hospital benefit period
  • Cost sharing: Daily copayments after day 60 for inpatient hospital care (out of a maximum of 150 covered days); daily copayments after day 20 for skilled nursing facility care (out of a maximum of 100 covered days)

Part B:

  • Deductible: $283 annual
  • Cost sharing: 20% coinsurance for most Part B-covered services

Cost Sharing for Part A Services

Inpatient hospital services covered under Medicare Part A are subject to a deductible of $1,736 in 2026, which applies per benefit period rather than per year, meaning that some beneficiaries may pay the deductible more than once if they are hospitalized multiple times in a year. Cost sharing only applies after the first 60 days of a hospital stay, at a rate of $434 per day for days 61-90 and $868 for each additional day afterwards in 2026 (up to a lifetime cap of 60 additional days).

For a stay in a skilled nursing facility following a qualifying hospitalization, beneficiaries pay no cost sharing for the first 20 days and $217 per day for days 21-100 in 2026. Medicare covers a maximum of 100 days of skilled nursing facility care per benefit period, after which point beneficiaries are responsible for the full cost of any additional days. Other Part A services, such as hospice care or home health services, are covered with no deductible and no cost sharing (with the exception of certain services, such as pain management medications and respite care, for which modest cost sharing may apply).

Cost Sharing for Part B Services

Services covered under Medicare Part B, such as doctor visits, outpatient hospital services, diagnostic tests and imaging, mental health and substance use disorder services, and durable medical equipment (e.g., prosthetics or mobility devices) are generally subject to an annual deductible of $283 in 2026 and a coinsurance rate of 20%. Many preventive services, such as annual wellness visits, flu shots and certain other vaccines, mammograms, and prostate cancer screenings are covered with no deductible or coinsurance.

Traditional Medicare has No Out-of-Pocket Limit

Traditional Medicare does not include an annual limit on how much beneficiaries pay out-of-pocket for Part A and Part B services. For this reason, many beneficiaries choose to purchase a Medigap policy, which helps cover Part A and B cost-sharing requirements in traditional Medicare, offering beneficiaries protection against unforeseen or catastrophic out-of-pocket expenses. Beneficiaries who choose to purchase a Medigap policy must pay a separate monthly premium to their Medigap insurer (in addition to the Part B premium). The average premium among current Medigap policyholders was $217 per month in 2023 (or $2,604 for the year), though Medigap premiums may rise with age and other factors, with considerable variation by state and policy type.

In addition to Medigap, some beneficiaries have access to other types of supplemental coverage, such as employer- or union-sponsored coverage or Medicaid coverage, which may also assist with out-of-pocket expenses, as well as coverage of services not included in traditional Medicare. Beneficiaries with low incomes and modest assets who do not qualify for full Medicaid coverage may still qualify for help from their state Medicaid program to cover Medicare Part A and Part B deductibles and cost-sharing requirements (as well as premium costs, as noted above).

Costs Under Medicare Advantage

Plan Premium: Varies by plan; 75% pay no additional premium

Deductible: Varies by plan; many plans do not include a deductible

Cost Sharing: Varies by plan, subject to a maximum out-of-pocket cap of $9,250 for in-network services or $13,900 for all covered services

Medicare Advantage plans are private health plans that contract with Medicare to provide Part A and Part B benefits, and serve as an alternative to traditional Medicare. Most Medicare Advantage plans also include prescription drug coverage and offer supplemental benefits not covered in traditional Medicare, such as dental, vision, and hearing services. Medicare Advantage plans often have lower cost-sharing requirements for many services than what beneficiaries would face in traditional Medicare. At the same time, Medicare Advantage plans frequently use provider networks, prior authorization, and referral requirements to manage enrollees’ use of services, in contrast to traditional Medicare where these types of restrictions are rarely used.

Premiums

People in Medicare Advantage plans are required to pay the standard monthly Part B premium, plus the income-related surcharge as applicable, and the Part A premium if they do not qualify for premium-free Part A, as well as any additional premium charged by their Medicare Advantage plan. However, most Medicare Advantage enrollees are in plans with no additional plan premium. Among Medicare Advantage plans that include prescription drug coverage (known as MA-PDs) available for individual enrollment, the average enrollment-weighted premium is $15 per month in 2026. This amount is heavily weighted by zero-premium plans, as three-quarters (75%) of all MA-PD enrollees are in plans that charge no monthly premium.

Some Medicare Advantage plans use rebate dollars from Medicare payments to buy down a portion of the monthly Part B premium for their enrollees. In 2026, roughly one third (31%) of all MA-PD enrollees are in plans that reduce the Part B premium, most often by less than $10 per month.

Cost Sharing for Part A and Part B Services

Medicare Advantage plans are required to cover all services covered under Medicare Parts A and B. Overall cost sharing in Medicare Advantage cannot exceed what would be paid across Part A and Part B services in traditional Medicare, though specific cost-sharing requirements vary across plans and may be higher or lower for a given service, with some exceptions. Cost-sharing requirements may also vary depending on whether or not a given provider or health care facility is included in the plan’s network. Preferred provider organizations (PPOs) generally offer coverage of out-of-network services but may require higher cost sharing than would be required for in-network services, while health maintenance organizations (HMOs) do not include any coverage of out-of-network services.

Among an illustrative sample of six high-enrollment Medicare Advantage plans available in 2026, representing five of the largest insurers in six different states across the country, none of the six plans required an additional premium or a deductible for medical services covered under Medicare Part A and Part B, but plan costs for Part A and Part B services varied widely (Figure 2).
Cost Sharing for Medicare Covered Services Varies Across Six High-Enrollment Medicare Advantage Plans (Table)
  • Inpatient hospitalization: Among the three PPOs examined, daily copays for inpatient services at in-network facilities ranged from $330 per day for days 1-7 to $550 per day for days 1-5, after which no additional cost sharing was required, while coinsurance for inpatient services at out-of-network facilities ranged from 40% to 50% for all covered days. Among the three HMOs examined, daily copays for inpatient services ranged from $0 for all days to $275 for days 1-8, after which no additional cost sharing was required.
  • Primary care visits: Among the three PPOs examined, copays for primary care visits ranged from $0 to $5 for in-network providers and from $45 to a 50% coinsurance fee for out-of-network providers. None of the three HMOs examined charged a copay for primary care visits.
  • Specialty care visits: Among the three PPOs examined, copays for specialty care visits ranged from $35 to $60 for in-network providers and from $95 to a 50% coinsurance for out-of-network providers. Among the three HMOs examined, copays for specialty care visits ranged from $0 to $30.
  • Outpatient hospital services: Among the three PPOs examined, copays for outpatient services at in-network facilities ranged from $0 for select services (such as colonoscopies) to $550 for most covered services, while coinsurance for outpatient services at out-of-network facilities ranged from 40% to 50%. Among the three HMOs examined, copays for outpatient services ranged from $0 to $275 for most services.

Out-of-Pocket Limits are Required in Medicare Advantage

Medicare Advantage plans are required to include a limit on enrollees’ out-of-pocket spending. In 2026, this limit may not exceed $9,250 for in-network services or $13,900 for all covered services, though plans may choose to offer limits below these amounts. The average out-of-pocket limit among Medicare Advantage enrollees in 2026 is $5,421 for in-network services (across HMOs and PPOs) and $9,825 for in- and out-of-network services combined (among PPOs, as HMOs do not include coverage of out-of-network services). Just over one in ten (13%) Medicare Advantage enrollees are in plans with limits of $3,000 or less for in-network services, while one in five (19%) are in plans with limits greater than $7,000. Among PPO enrollees, roughly, one in ten (9%) are in plans with limits of $6,000 or less for in-network and out-of-network services combined, while one in four (25%) are in plans with limits greater than $12,000. Out-of-pocket limits apply to Part A and Part B services only, though out-of-pocket spending for Part D drugs is subject to a separate limit (as discussed below).

Out-of-pocket limits varied among the six illustrative plans described above. Among the three PPOs examined, out-of-pocket limits ranged from $5,200 to $6,700 for in-network services and from $10,000 to $10,100 for in-network and out-of-network services combined. Among the three HMOs examined, out-of-pocket limits ranged from $699 to $3,850 for covered services.

Non-Medicare Covered Services

Most Medicare Advantage plans include some coverage of services not covered in traditional Medicare, such as dental care, glasses and eye exams, and hearing exams or hearing aids. The scope of coverage for these benefits varies widely between plans, with some limited to coverage of basic preventive services (e.g., dental cleanings) while others offer a broader range of covered services (e.g., root canals or dentures). Cost sharing for these benefits also varies between plans, and coverage may be subject to network restrictions, limits on the number of services covered per year, or annual dollar caps on the amount the plan will pay towards covered services.

Costs for Part D Prescription Drug Coverage

Premium: Varies by plan; income-related adjustments apply for people with higher incomes

Deductible: $615 (standard); plans can lower or eliminate the deductible

Cost Sharing: Varies by plan, subject to an annual out-of-pocket cap of $2,100

Medicare Part D is a voluntary outpatient prescription drug benefit for people with Medicare provided through private plans that contract with the federal government. Beneficiaries can choose to enroll in either a stand-alone prescription drug plan (PDP) to supplement traditional Medicare or a Medicare Advantage drug plan (MA-PD) that includes drug coverage and all other Medicare-covered benefits. Monthly premiums, deductibles, cost-sharing requirements for covered drugs, pharmacy networks, and formularies (the list of drugs covered by a plan) all vary across Part D plans.

Part D Premiums

Many, though not all, Part D enrollees pay a monthly premium for Part D coverage, with premiums varying by plan. In 2026, the average Part D premium among stand-alone PDPs is $36 per month. For MA-PD enrollees, the Part D premium is included as a portion of their Medicare Advantage plan premium. In 2026, the Part D portion of the average MA-PD premium is $8 per month, but 75% of Medicare Advantage enrollees in individual plans pay no premium for Part D coverage (because the Medicare Advantage insurer uses payments from the federal government to buy down these costs).

As with the Part B premium, beneficiaries with incomes greater than $109,000 for individuals or $218,000 for married couples in 2026 pay a higher, income-adjusted Part D premium, with monthly adjustment amounts ranging from $14.50 to $91.00 added to their individual Part D plan’s premium. Beneficiaries with low incomes and modest assets can qualify for financial assistance through the Part D Low-Income Subsidy (LIS). People who qualify for the LIS program pay modest copayments for prescription drugs, no drug deductible, and no premium for drug coverage if they are enrolled in premium-free “benchmark” plans.

Late enrollment penalty. Beneficiaries who go without Part D coverage for 63 days or more at any point after their initial enrollment period and lack other qualifying drug coverage in the interim are subject to a late enrollment penalty. The Part D late enrollment penalty is a lifetime penalty equal to 1% of the Part D base beneficiary premium ($38.99 in 2026) for each month of delayed coverage. For example, someone who went without Part D or equivalent coverage for eighteen months would face an 18% monthly Part D premium penalty and would pay $7 per month in 2026 in addition to any premium charged by their Part D plan (based on $38.99 times 18%).

Cost Sharing

The standard Part D deductible is $615 in 2026, but Part D plans can offer an enhanced benefit with a lower or no deductible. In 2026, MA-PD enrollees face an average Part D deductible of $371, while PDP enrollees face an average deductible of $544. Part D plans typically charge different amounts for covered drugs, with lower cost-sharing amounts charged for generic drugs and preferred brands and higher cost-sharing amounts for non-preferred and specialty drugs. Cost sharing typically consists of a mixture of flat dollar copays and coinsurance (based on a percentage of the drug’s list price). Part D plans can also designate certain pharmacies where enrollees will face lower (“preferred”) cost-sharing requirements.

In 2026, the median copay for generic drugs is $3 among PDPs and $5 among MA-PDs. For preferred brand drugs, the median copay is $45 among PDPs and $47 among MA-PDs. Virtually all PDP enrollees pay coinsurance for non-preferred drugs (with a median rate of 34%), while MA-PDs may charge either coinsurance (with a median rate of 38%) or a flat dollar copay (with a median of $100). The median coinsurance rate for specialty drugs is 25% among PDPs and 28% among MA-PDs (Figure 3).
Cost-Sharing Requirements Vary by Formulary Tier Among PDPs and MA-PDs (Split Bars)

An Out-of-Pocket Limit Applies Under Part D

Out-of-pocket costs for Part D enrollees are capped at $2,100 in 2026. Once this out-of-pocket limit is reached, enrollees pay no additional costs for the remainder of the year for drugs covered by their Part D plan. Part D enrollees in plans that offer enhanced benefits could pay less than $2,100 out of pocket before they qualify for catastrophic coverage. Part D enrollees also have the option of spreading out their out-of-pocket costs over a calendar year to lower their monthly costs.

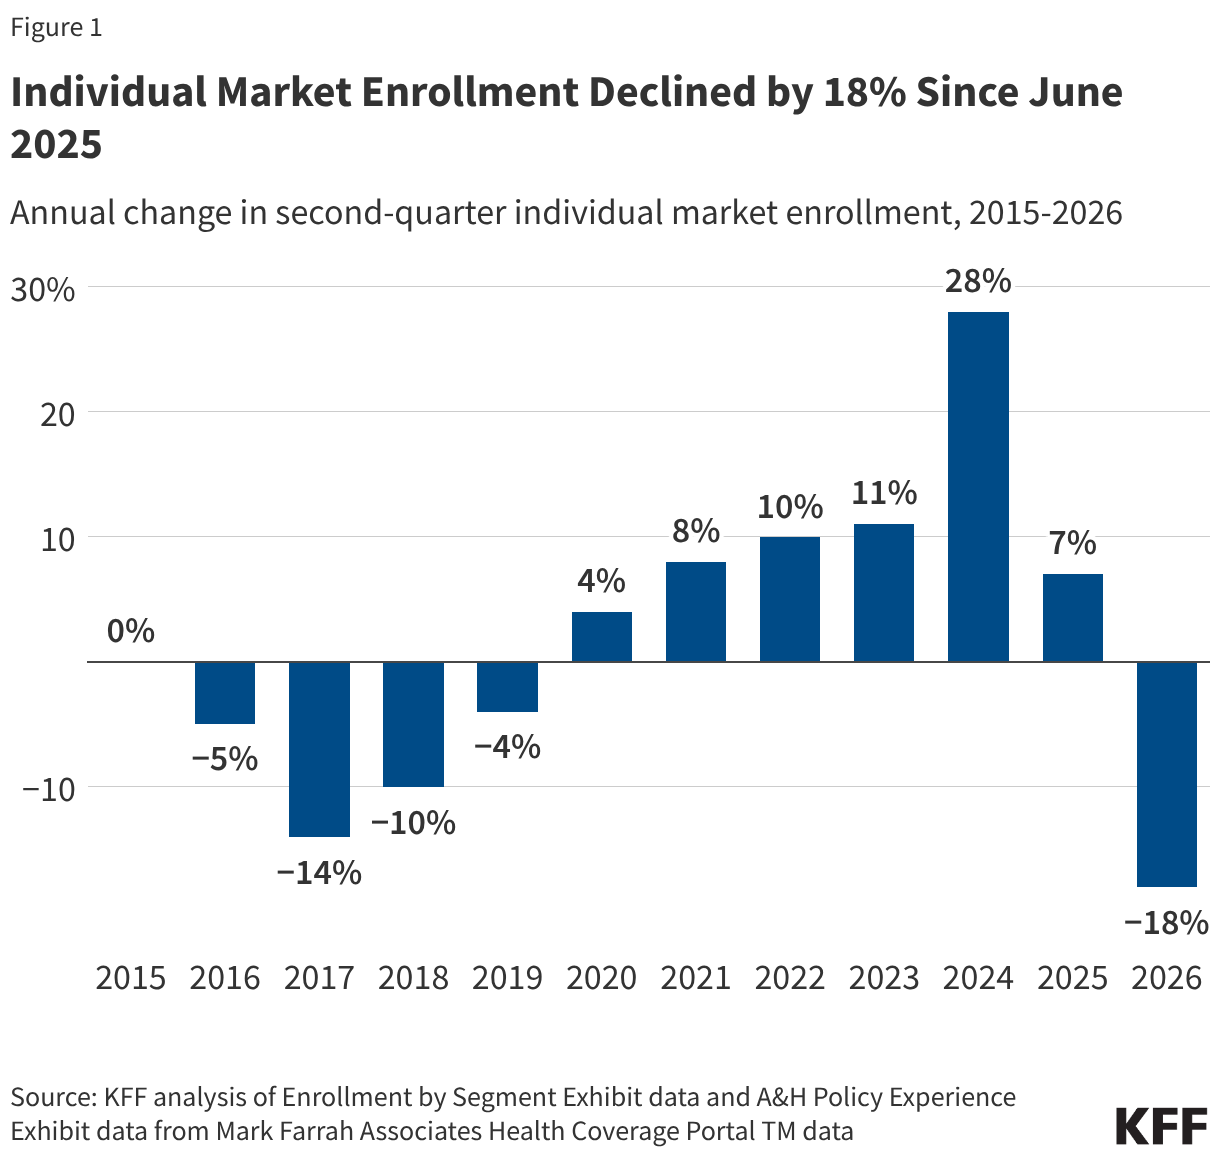
Medicare Advantage Plan Availability Varies Widely by County for 2027

One in five (20%) Medicare beneficiaries have more than 40 Medicare Advantage drug plan options, while 1% of beneficiaries have none.

Published: Oct 9, 2026

The Medicare Advantage market, the private plan alternative to traditional Medicare, is dynamic, and plan offerings can change from year to year. With 28 Medicare Advantage prescription drug (MA-PD) plans available to the average beneficiary in 2027, most people with Medicare have a robust set of MA-PD options. However, Medicare Advantage plans are offered at the county level, and variation in plan availability across the country has long been a feature of the Medicare Advantage market. This analysis uses Medicare plan landscape data from the Centers for Medicare & Medicaid Services to examine county-level variation in MA-PD plan availability in 2027 and changes from 2026. This analysis does not examine changes in costs, benefits, or other plan characteristics. The analysis shows that plan level availability varies widely across the country in 2027, with a modest reduction in the share of enrollees having more than 40 MA-PDs to choose from compared to 2026, and some major insurers exiting a much larger number of counties than they are entering.

Findings

One in five Medicare beneficiaries (20%) can choose from more than 40 MA-PDs for coverage in 2027.

The 20% of Medicare beneficiaries who have more than 40 MA-PD options are concentrated in 4% of counties (Figure 1). This is a decrease from 2026 when 27% of beneficiaries, who resided in 6% of counties, had more than 40 options. Similar to 2026, the counties with the most plan options are predominantly in Pennsylvania, Ohio, and Michigan, as well as Los Angeles County, California. Beneficiaries in Lancaster, Pennsylvania can choose from 66 MA-PDs – the most offerings of any county in the U.S.

One in Five Medicare Beneficiaries (20%) Have More Than 40 Medicare Advantage Plans with Prescription Drug Coverage Available Where They Live in 2027 (Choropleth map)

For 2027, Medicare beneficiaries residing in 193 counties will have no MA-PDs available for general enrollment, an increase from 123 counties in 2026.

Beneficiaries in the 193 counties without any MA-PD option for general enrollment for 2027 comprise 1% of all Medicare beneficiaries, or 638,000 people. This is an increase from 2026, when 399,000 beneficiaries did not have an MA-PD option (an increase of 239,000 beneficiaries).

The counties with no MA-PD options are located in 16 states (Alaska, California, Colorado, Idaho, Kansas, Minnesota, Montana, Nebraska, Nevada, New Hampshire, North Dakota, Oklahoma, Oregon, South Dakota, Utah, and Vermont) and U.S. territories other than Puerto Rico. These are the same states as 2026, with the addition of New Hampshire, North Dakota, and Oklahoma. Similar to 2026, there are no MA-PDs for general enrollment being offered in any county in Alaska in 2027, which includes about 110,000 beneficiaries.

In six counties (Boyd, Nebraska; Aurora, Beadle, Bon Homme, Brown, and Charles Mix, South Dakota) there is a Medicare Advantage plan option without prescription drug coverage, but in the other 187 counties, no Medicare Advantage plans with or without prescription drug coverage for general enrollment are available. In some counties where Medicare Advantage plans for general enrollment are not available, there are other private plan options, including cost plans as well as special needs plans, which restrict enrollment to Medicare beneficiaries who meet specific criteria.

The two largest Medicare Advantage insurers – UnitedHealth Group and Humana – are exiting more counties, meaning they are no longer offering any MA-PDs in those counties, than they are entering in 2027.

UnitedHealth Group is exiting 228 counties and entering 9 new counties, and Humana is exiting 62 counties and entering 4 new counties (Figure 2). Humana is offering MA-PDs in the largest number of counties relative to other insurers - about 80% of all U.S. counties, similar to 2026 - while UnitedHealth Group is offering plans in about 70% of counties, a decline from 2026, when the insurer offered plans in nearly 80% of counties.

In 2027, 10 Medicare Advantage Insurers are Making Changes to Plan Offerings that Affect at Least 50 Counties (Table)

Among insurers offering MA-PD plans, Health Care Service Corporation is making the largest reduction in its county footprint, exiting the greatest number of counties in 2027 (498 counties) while entering no new counties. Centene has the second largest reduction, exiting 359 counties and entering 15 new counties for 2027. Blue Cross Blue Shield of Michigan Mutual Ins. Co., which had offered MA-PDs in Iowa, Michigan, North Dakota, South Dakota, and Wyoming in 2026, is exiting 177 counties and entering one new county, and will only offer MA-PDs in Michigan and Wyoming for 2027. Elevance Health is exiting 66 counties and entering 10 new counties in 2027.

Two insurers - Group 1001 (marketed as Clear Spring Health), which offered plans in Colorado, Georgia and Illinois, and Molina Healthcare – are completely exiting the MA-PD market, though Molina is still offering SNPs in many counties in 2027.

In contrast, Devoted Health is expanding its MA-PD footprint, entering 342 counties and exiting none in 2027. Second to Devoted Health, CVS Health is entering a larger number of new counties in 2027 than other insurers (63 new counties), but is also exiting 186 counties.

Kaiser Foundation Health Plans, a high enrollment insurer, is maintaining its footprint, exiting three counties while entering three new ones in 2027 (data not shown).

The characteristics of markets that insurers are leaving vary. In some cases, multiple insurers are exiting more rural areas with relatively small Medicare populations, such as four counties in Minnesota (Brown, Lake of the Woods, Morrison, and Renville), in each of which three insurers who offered MA-PDs in 2026 are no longer offering MA-PDs for 2027. In other cases, individual insurers are exiting counties in more urban areas with higher Medicare Advantage penetration, such as Miami-Dade County, FL where Health Care Service Corporation is no longer offering MA-PDs in 2027 and Monroe County, New York (Rochester) where Humana left the market. The different decisions of insurers to exit certain counties suggest a combination of factors are at play, including local market characteristics, cost pressures, shifts in firm-level strategies, and ultimately the insurers’ assessment of profitability.