News Release

Analysis: Prices for Many Brand-Name TrumpRx Drugs Are Cheaper than the Average Price in Other Wealthy Countries, But Are Almost as Likely To Be More Expensive

Published: Sep 24, 2026

Consumers who buy brand-name prescription drugs without an available generic or biosimilar at the prices available through the new TrumpRx website are about as likely to pay more as pay less for those drugs relative to the publicly listed prices available in other comparatively wealthy countries, a new KFF analysis finds.

The Trump administration has promoted the TrumpRx website as a way for consumers to get the lowest prices for prescription medications in the world, drawing on voluntary pricing agreements with drug manufacturers aimed at securing “Most Favored Nation” prices for American consumers. For many brand-name drugs listed on the website, TrumpRx directs consumers to manufacturers’ discount coupons to get the drugs at a pharmacy without using insurance.

The analysis compares the prices of 32 brand-name drugs listed on the TrumpRx website with those in other countries. Key findings include:

  • For 17 of the 32 drugs, the TrumpRx price is lower than the average price in comparable countries. This includes five drugs for which the TrumpRx price is lower than the prices available in any of the other countries. Eight drugs have a price that is $100 less than the average in other countries.
  • For the other 15 drugs, the TrumpRx price is higher than the average price in comparable countries. This includes 13 drugs for which the TrumpRx price is higher than prices available in any of the other countries.
  • There are wide variations in the price differences between TrumpRx and other countries. For nine of the drugs, the prices on TrumpRx are at least double the average across other countries. This includes Enbrel, a drug used to treat rheumatoid arthritis; the TrumpRx price is $2,725 higher than the average across other countries ($3,354 versus $641).

This analysis compares the TrumpRx drug prices with available prices in Australia, Austria, Belgium, Canada, France, Germany, Japan, the Netherlands, Sweden, Switzerland, and the United Kingdom for the brand-name drugs listed on the TrumpRx site (as of August 25, 2026) that do not have generics or biosimilars available in the U.S. and that had publicly available prices in at least one of the other nations. It does not compare the prices available on TrumpRx now to the prices that may have been available to consumers in the U.S. prior to its launch.

There is no one source of data for drug prices in other countries. In many cases, the publicly listed prices used in the analysis represent the price paid by the government’s national health system, or similar entity, and not necessarily what a consumer living in the country and covered by its health system would pay.

The analysis also examines some of the factors that contribute to differences in prices across countries and through TrumpRx, including the role of government in setting drug prices. The analysis is available through the Peterson-KFF Health System Tracker, an online hub monitoring how well the U.S. health system is operating through cost and quality measures.

VOLUME 55

KFF Women’s Health Survey Explores How Women Navigate Contraceptive Information


Highlights

The 2026 KFF Women’s Health Survey finds that health care providers remain the most trusted source of reliable health information for reproductive-age women. Large shares, though, also report using online sources and social media, and many report being exposed to false or misleading information that can lead to changes in contraceptive use, like starting, changing, or stopping a birth control method.

And as AI tools become more embedded in health care and government, some institutions are developing new AI governance policies around their use, but most government AI policies do not address health, and those that do are largely not public. One Ohio health department’s new AI policy offers a rare look at a health-specific policy, explicitly addressing accuracy and public trust.


KFF Women’s Health Survey Explores Trusted Sources of Information and Exposure to Contraceptive Misinformation

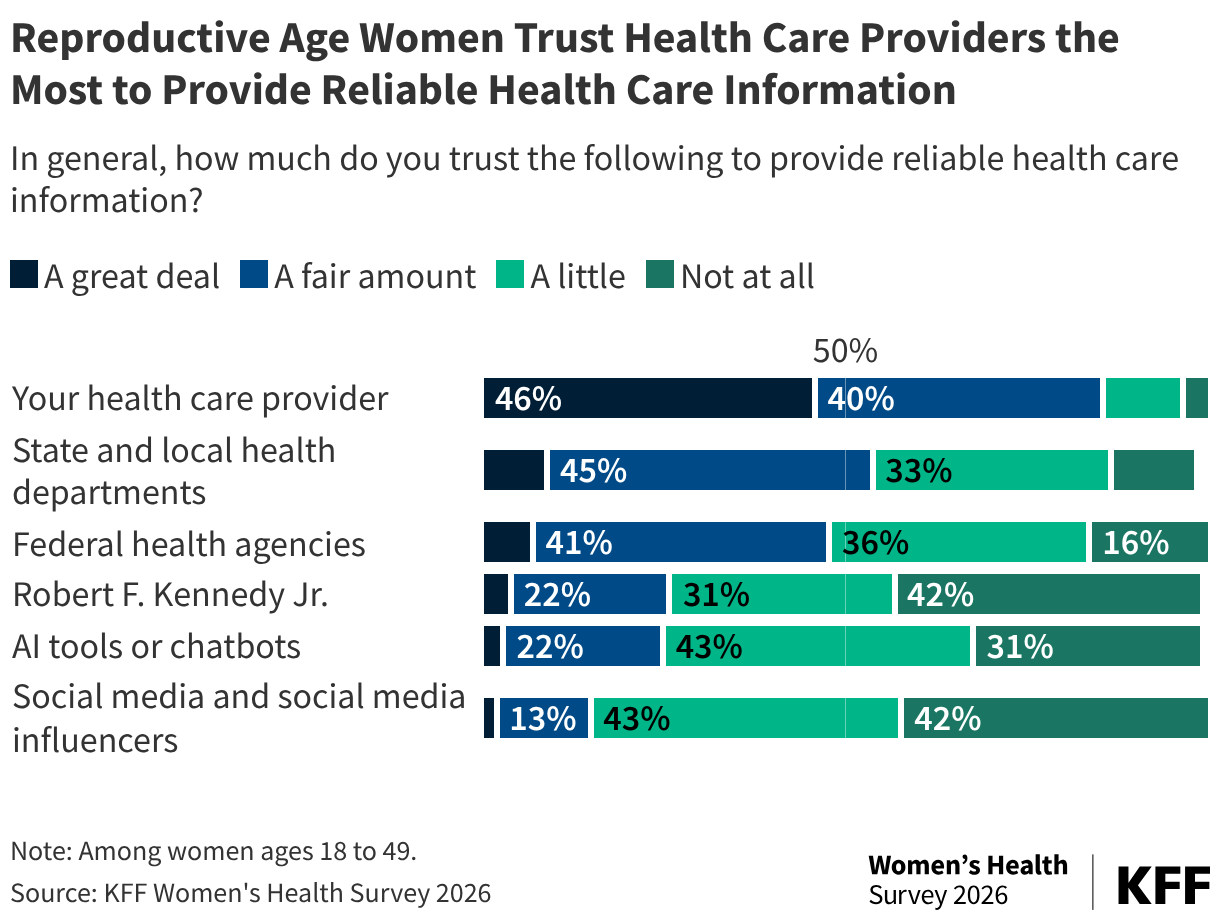
Health care providers remain the most trusted source for reliable health information among reproductive-age women ages 18 to 49. According to the 2026 KFF Women’s Health Survey, more than eight in ten (86%) reproductive-age women said they trust health care providers “a great deal” or “a fair amount” for reliable information, compared with a quarter (25%) who said the same about AI tools and chatbots and fewer (15%) about social media and social media influencers. These findings largely mirror KFF polling among the general public, which has found similarly high trust in doctors and relatively lower trust in AI chatbots for health information.

Figure 3 is a stacked horizontal bar chart titled "Reproductive Age Women Trust Health Care Providers the Most to Provide Reliable Health Care Information" with "A great deal" colored dark blue, "A fair amount" colored blue, "A little" colored green, and "Not at all" colored dark green. The majority of women ages 18 to 49 trust their health care provider and state and local health departments a great deal or fair amount to provide reliable health care information. Women trust social media and AI tools or chatbots the least to provide reliable health care information, with majorities of women also having little trust in federal health agencies and Robert F. Kennedy Jr.

Still, use of online sources for health information is widespread despite this limited trust. A majority (87%) report looking for health information or advice online through internet search engines, social media, or AI tools. Many reproductive-age women report seeing information about contraception on social media, regardless of whether they were looking for it. About a third (35%) say they’d seen or heard something about contraception on social media in the past year, rising to four in ten (42%) among younger women ages 18 to 25.

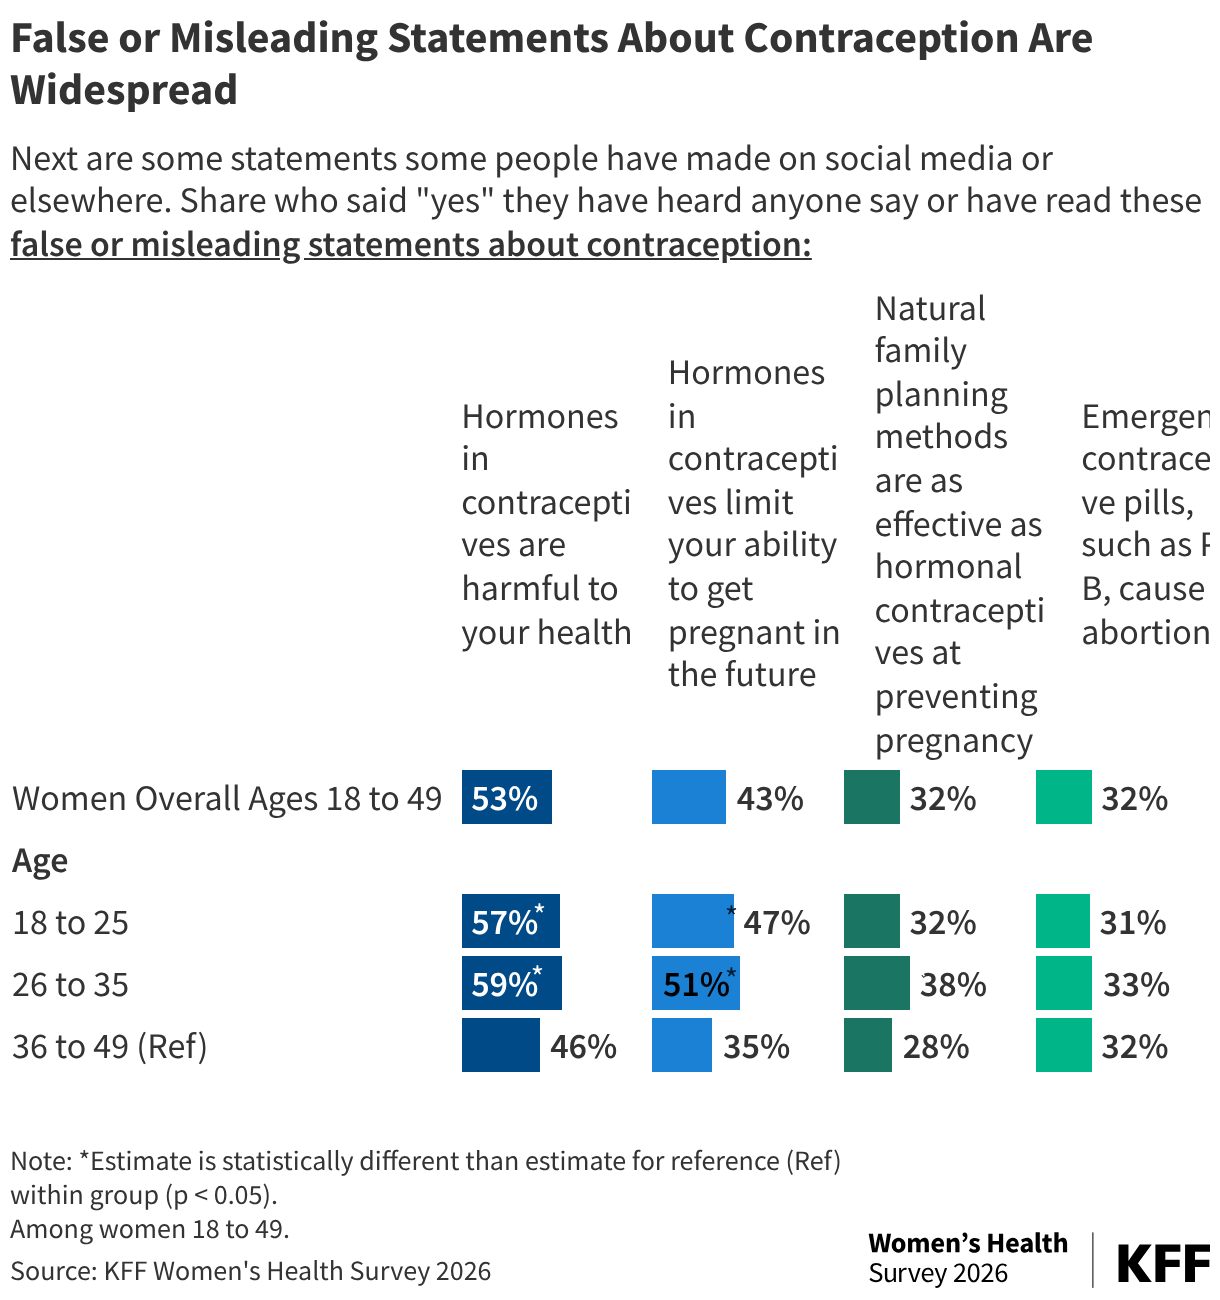
Many reproductive-age women also report being exposed to false and misleading statements about contraception on social media and elsewhere. About half (53%) of reproductive-age women say they’ve heard the false claim that hormonal contraceptives are harmful to your health, and four in ten (43%) have encountered the incorrect claim that they limit your ability to get pregnant in the future. Both of these claims are contradicted by current evidence. Roughly a third (32%) have seen false claims that natural family planning is as effective as hormonal contraception at preventing pregnancy and that emergency contraceptive pills, such as Plan B, cause abortions, neither of which is accurate.

False or Misleading Statements About Contraception Are Widespread (Split Bars)

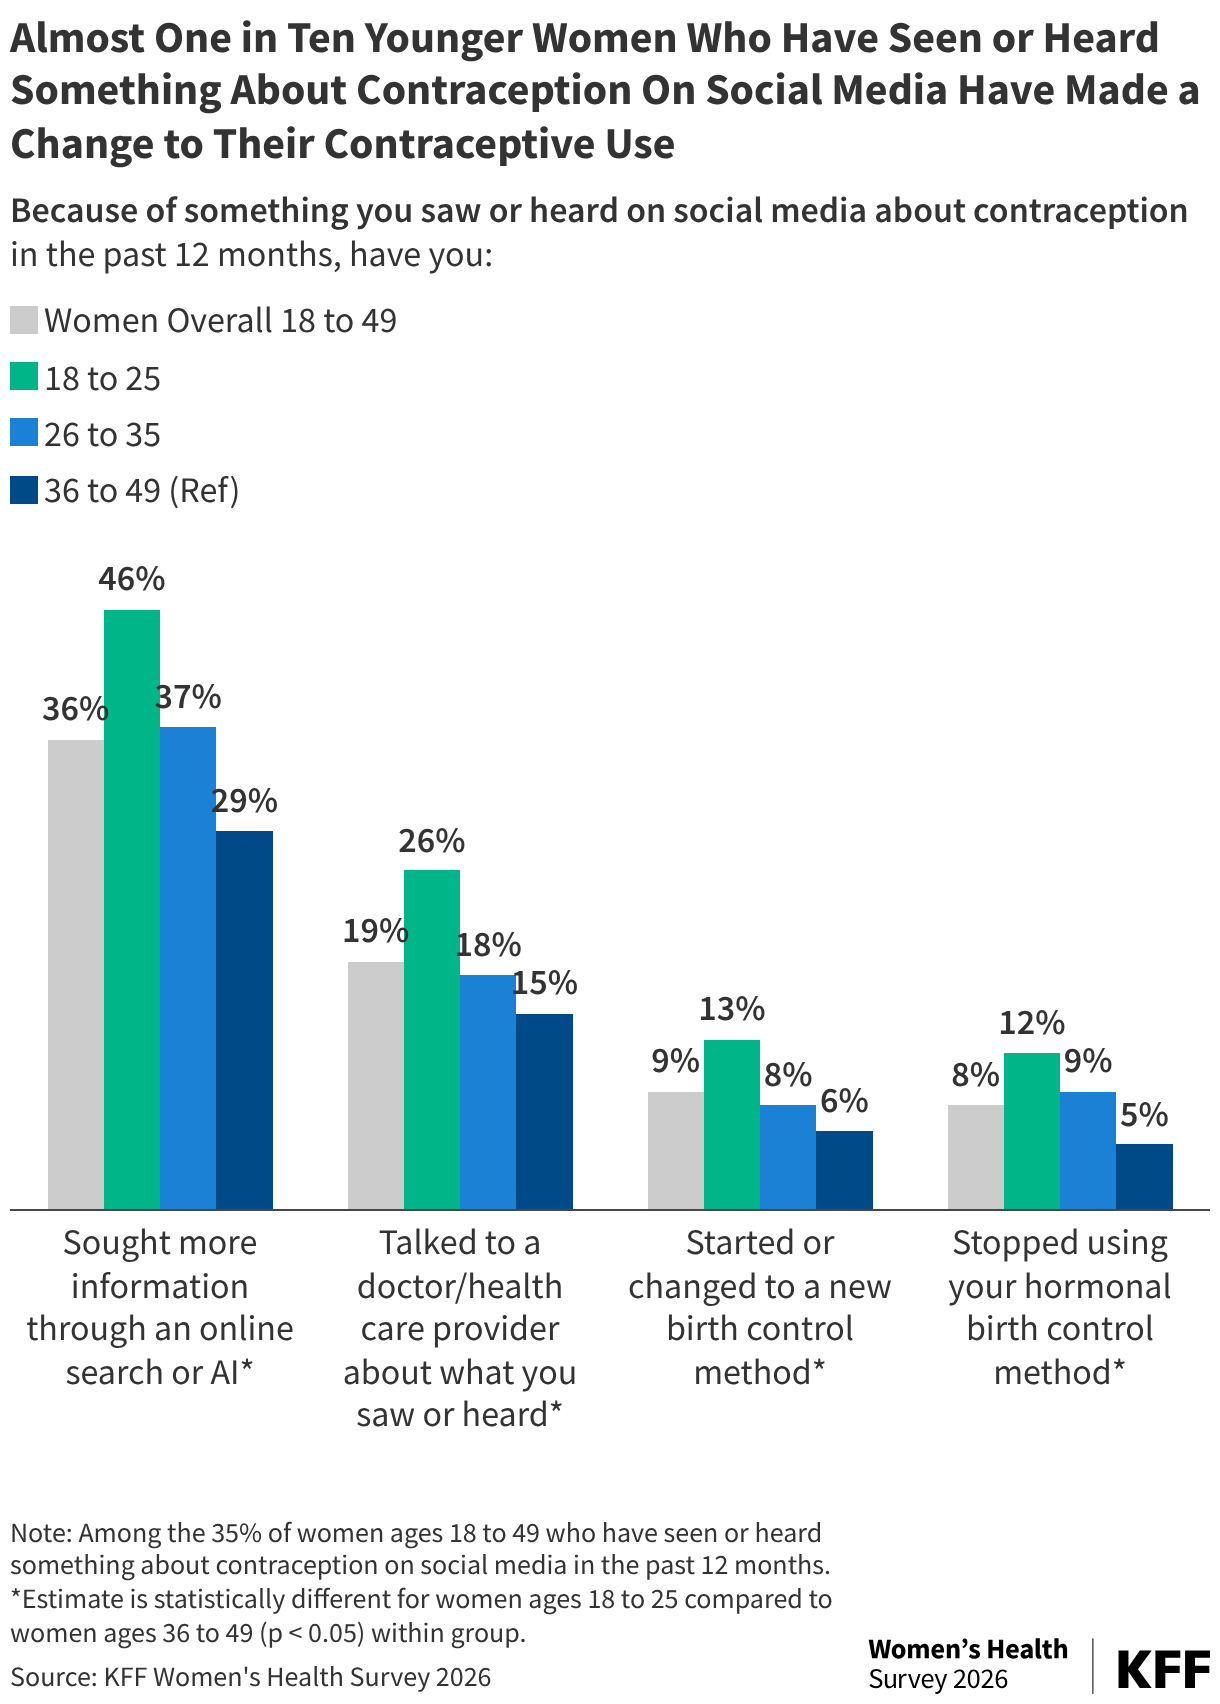
Among women who saw contraception-related content on social media, more than a third (36%) went on to search for more information online, one in five (19%) talked to a doctor about what they’d seen, and about one in ten either started or changed to a new birth control method (9%) or stopped using their hormonal birth control (8%) because of what they’d seen, with higher shares of young women ages 18 to 25 doing each of these.

A grouped vertical bar chart titled "One in Ten Younger Women Who Have Seen Something About Contraception On Social Media Have Made a Change to Their Contraceptive Use" and shows women overall ages 18 to 49 in gray, women ages 18 to 25 in green, women ages 26 to 35 in blue, and women ages 36 to 49 in dark blue. Among women who have seen or heard something on social media about contraception, one in three (36%) have sought more information through an online search or AI, one in five (19%) have talked talked to a doctor or health care provider about what they saw or heard, and one in ten (12%) have stopped using hormonal birth control or started or changed to a new birth control method. Higher shares of younger women ages 18 to 25 have done all of these things compared to women ages 36 to 49.

AI & Emerging Technology

Most State AI Policies Overlook Health-Specific Guidance, but One New Example Focuses on Accuracy and Trust

Questions about how generative AI tools could affect public trust and the accuracy of AI-generated information are among factors contributing to new governmental policies around AI use. According to an analysis of publicly available AI policies published last month by the Association of State and Territorial Health Officials (ASTHO), most of these plans focus on government-wide issues, such as data privacy and security, procurement, and vendor requirements. Some provisions, like requirements for human review and disclosure of AI use, may apply to health agencies within those jurisdictions. The analysis found, though, that few of the policies addressed health-specific applications directly, such as evaluating AI tools for disease surveillance or outbreak detection, and most health-specific policies that do exist are not public. 

One publicly available example from a health agency comes from the public health department of Ashland County, Ohio, which unanimously approved and released its own AI governance policy last month. The policy provides a look at how one health agency is approaching AI use, explicitly identifying public trust and the accuracy of AI-generated information as core considerations for the responsible use of AI in health care. The policy states that AI should be used in ways that “promote transparency, accountability, and community confidence.” Among other rules, staff are required to verify factual claims, citations, and statistics generated by AI before relying on them, and human review is required for most non-minor uses of AI to ensure accuracy. The policy also establishes an incident reporting framework for when AI-assisted work might include false information, treating errors where hallucinations enter published materials as incidents to be tracked and addressed. Beyond these general rules, the policy lays out health-specific approved AI use cases, including de-identified data analysis in epidemiology, health promotion content in nursing, and inspection communication templates in environmental health. It also states that no AI system may independently make clinical, regulatory, or public health decisions on behalf of the agency.

Because the Ashland County policy is publicly available, it offers the public, other health organizations, and researchers a look at how one health agency is trying to maintain accuracy and protect trust in its use of the technology, which has relatively low trust among the public overall for health information. KFF’s March 2026 Tracking Poll on Health Information and Trust found that a third of adults (33%) said they had a “great deal” or “fair amount” of trust in AI tools or chatbots to provide reliable information about health.

What to Watch Out For

As health agencies continue incorporating AI tools into their work and developing their own more tailored guidelines, could transparently communicating about their approaches to governing AI use impact public trust? More research on what the public expects from agencies using AI could help clarify how these policies might affect confidence in health agencies (which has declined since the COVID-19 pandemic) and the information they provide.

Some Medical Journals Are Responding to a Rise in AI-Generated Citations

Researchers have documented a rise in fabricated references across medical research, with some citations referencing studies that do not exist or do not support the claims attributed to them. One correspondence published earlier this year identified thousands of fake citations across millions of papers, with the rates climbing sharply after generative AI tools became widely available. Many of the references were difficult to distinguish from legitimate studies, pairing real authors and plausible titles with studies that were never published.

Some medical journals have begun to respond to the challenge of AI-fabricated citations, including by requiring disclosure when AI is used, but an analysis of 5,114 journals and over 5.2 million papers found that AI use without disclosure continues despite these policies. JAMA updated its guidance for authors last month in response to the journal’s own experience receiving manuscripts with inaccurate or nonexistent references and research showing that rates of author disclosure of AI use in submissions to their journal have remained low. Rather than requiring disclosure when AI contributes to references, JAMA’s approach advises against using AI to generate, format, or manage citations, and directs authors to standard reference managers instead.

Why This Matters

Fabricated citations carry the appearance of legitimate sourcing, making them difficult to catch without deliberate verification. Disclosure policies alone have not solved the problem, leading one major journal to move toward restricting AI’s use for generating references rather than asking authors to report it.


What We're Watching

As Trust in Federal Health Information Declines, Poll Suggests That Transparency and Data Can Make Information Seem Trustworthy

Public trust in information from the federal government has declined since 2024, according to a new survey from the AP-NORC Center for Public Affairs Research and USAFacts. The share of adults expressing “a great deal” or “quite a bit” of trust in federal information about health care has fallen ten points in the past two years, from 26% to 16%, with similar declines for federal information about the environment (21% to 12%), jobs and unemployment (25% to 15%), and elections and politics (22% to 13%). The findings mirror trends in KFF’s own polling on Health Information and Trust.

The NORC survey also points to what factors shape whether people consider information credible. When asked to rate the importance of various factors when considering whether information was factual, explaining how the information was gathered ranked highest, with seven in ten (71%) saying this was “extremely” or “very” important. Information presenting more than one viewpoint was also important to most adults (63%), as was not including opinions (56%).

A separate question asked how likely people would be to consider information factual given specific characteristics. Being based in data ranked highest, with six in ten (60%) saying that would be “extremely” or “very” likely to consider such information factual. Verification mattered too, though importance differed by source. About half (49%) said they would consider information factual if it was verified by scientists, while fewer said the same about academic institutions (39%) or the federal government (19%). The smallest shares said they would consider information factual if it was verified by AI chatbots (9%).

Why This Matters

As trust in federal health agencies continues to decline, health communicators may need to consider what factors could make their communication appear more credible. The NORC survey indicates that explaining how information was gathered or offering data-based verification may be effective in building credibility.

About The Health Information and Trust Initiative: the Health Information and Trust Initiative is a KFF program aimed at tracking health misinformation in the U.S., analyzing its impact on the American people, and mobilizing media to address the problem. Our goal is to be of service to everyone working on health misinformation, strengthen efforts to counter misinformation, and build trust. 


View all KFF Monitors

The Monitor is a report from KFF’s Health Information and Trust initiative that focuses on recent developments in health information. It’s free and published twice a month.

Sign up to receive KFF Monitor
email updates


Support for the Health Information and Trust initiative is provided by the Robert Wood Johnson Foundation (RWJF). The views expressed do not necessarily reflect the views of RWJF and KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities. The data shared in the Monitor is sourced through media monitoring research conducted by KFF.

Women’s Health Care Affordability Challenges

Findings from the 2026 KFF Women's Health Survey

Published: Sep 23, 2026

Affordability has dominated national conversations. High inflation rates, increased gas and grocery prices, and the constant rise in health care costs and insurance premiums have emerged as major political issues. Historically, national surveys find that many Americans report difficulties affording health care and have problems paying for health care services, particularly women, who have lower incomes, fewer financial resources, and use the health care system more than men. In recent years, people with health coverage have increasingly experienced difficulties affording care. The 2026 KFF Women’s Health Survey was fielded between March 11, 2026 to April 14, 2026 to better understand women’s experiences accessing and using health care services including barriers to care. The survey is a nationally representative survey of 4,688 women, ages 18 to 64, and 1,148 men, ages 18 to 64. This brief provides new information about the affordability challenges women report experiencing in the past 12 months and their impact on access and utilization of health care services.1

Key Findings

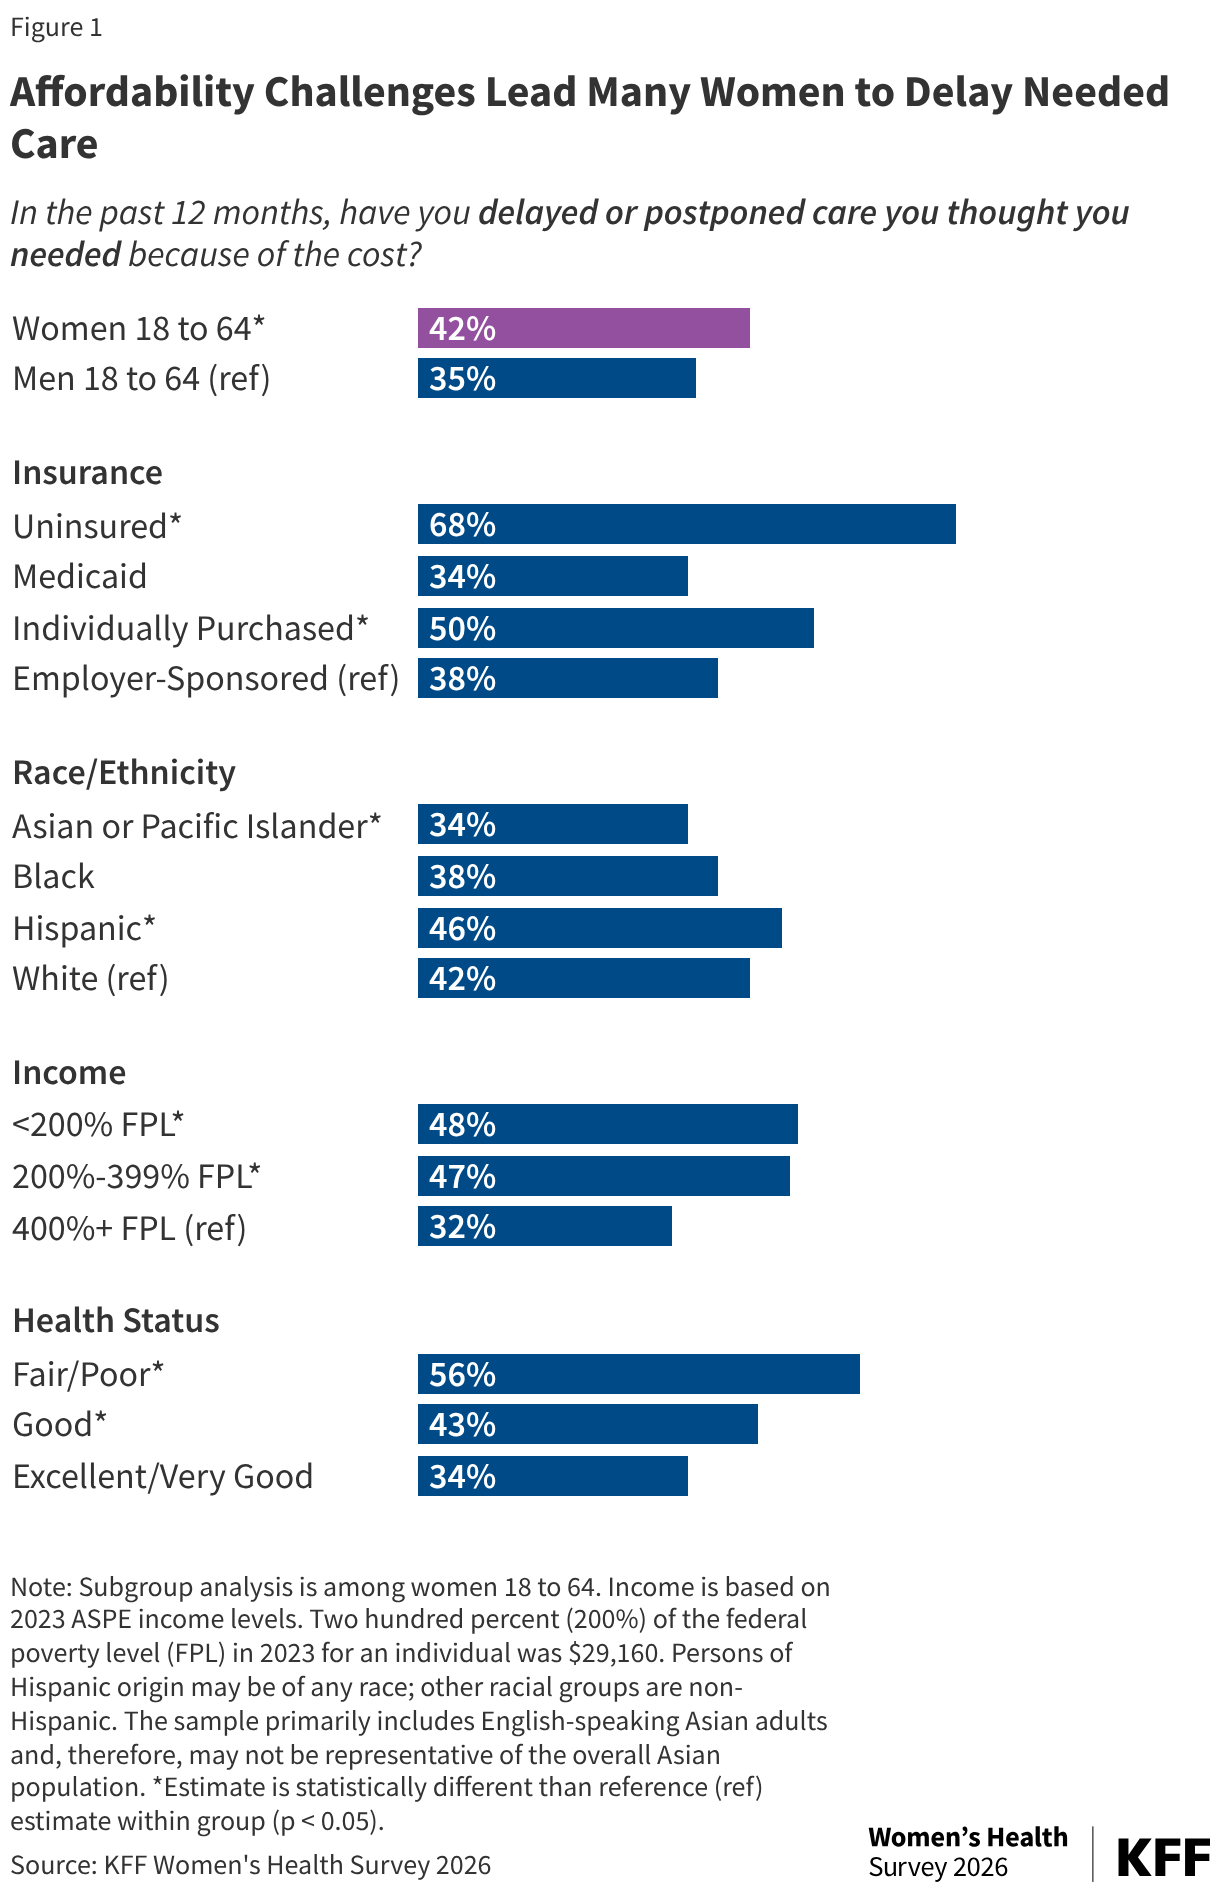
  • Many women, even those with insurance coverage, have delayed or postponed care they thought they needed in the past 12 months because of cost. Four in ten (42%) women, ages 18-64, and 35% of men, ages 18-64, report they have delayed or postponed care they thought they needed in the past year. While about two-thirds (68%) of uninsured women report putting off needed care due to costs, those with insurance are not immune from this problem. Half of women with individually purchased plans and a third of women with Medicaid (34%) and employer sponsored coverage (38%) report delaying or postponing needed care because of cost. 
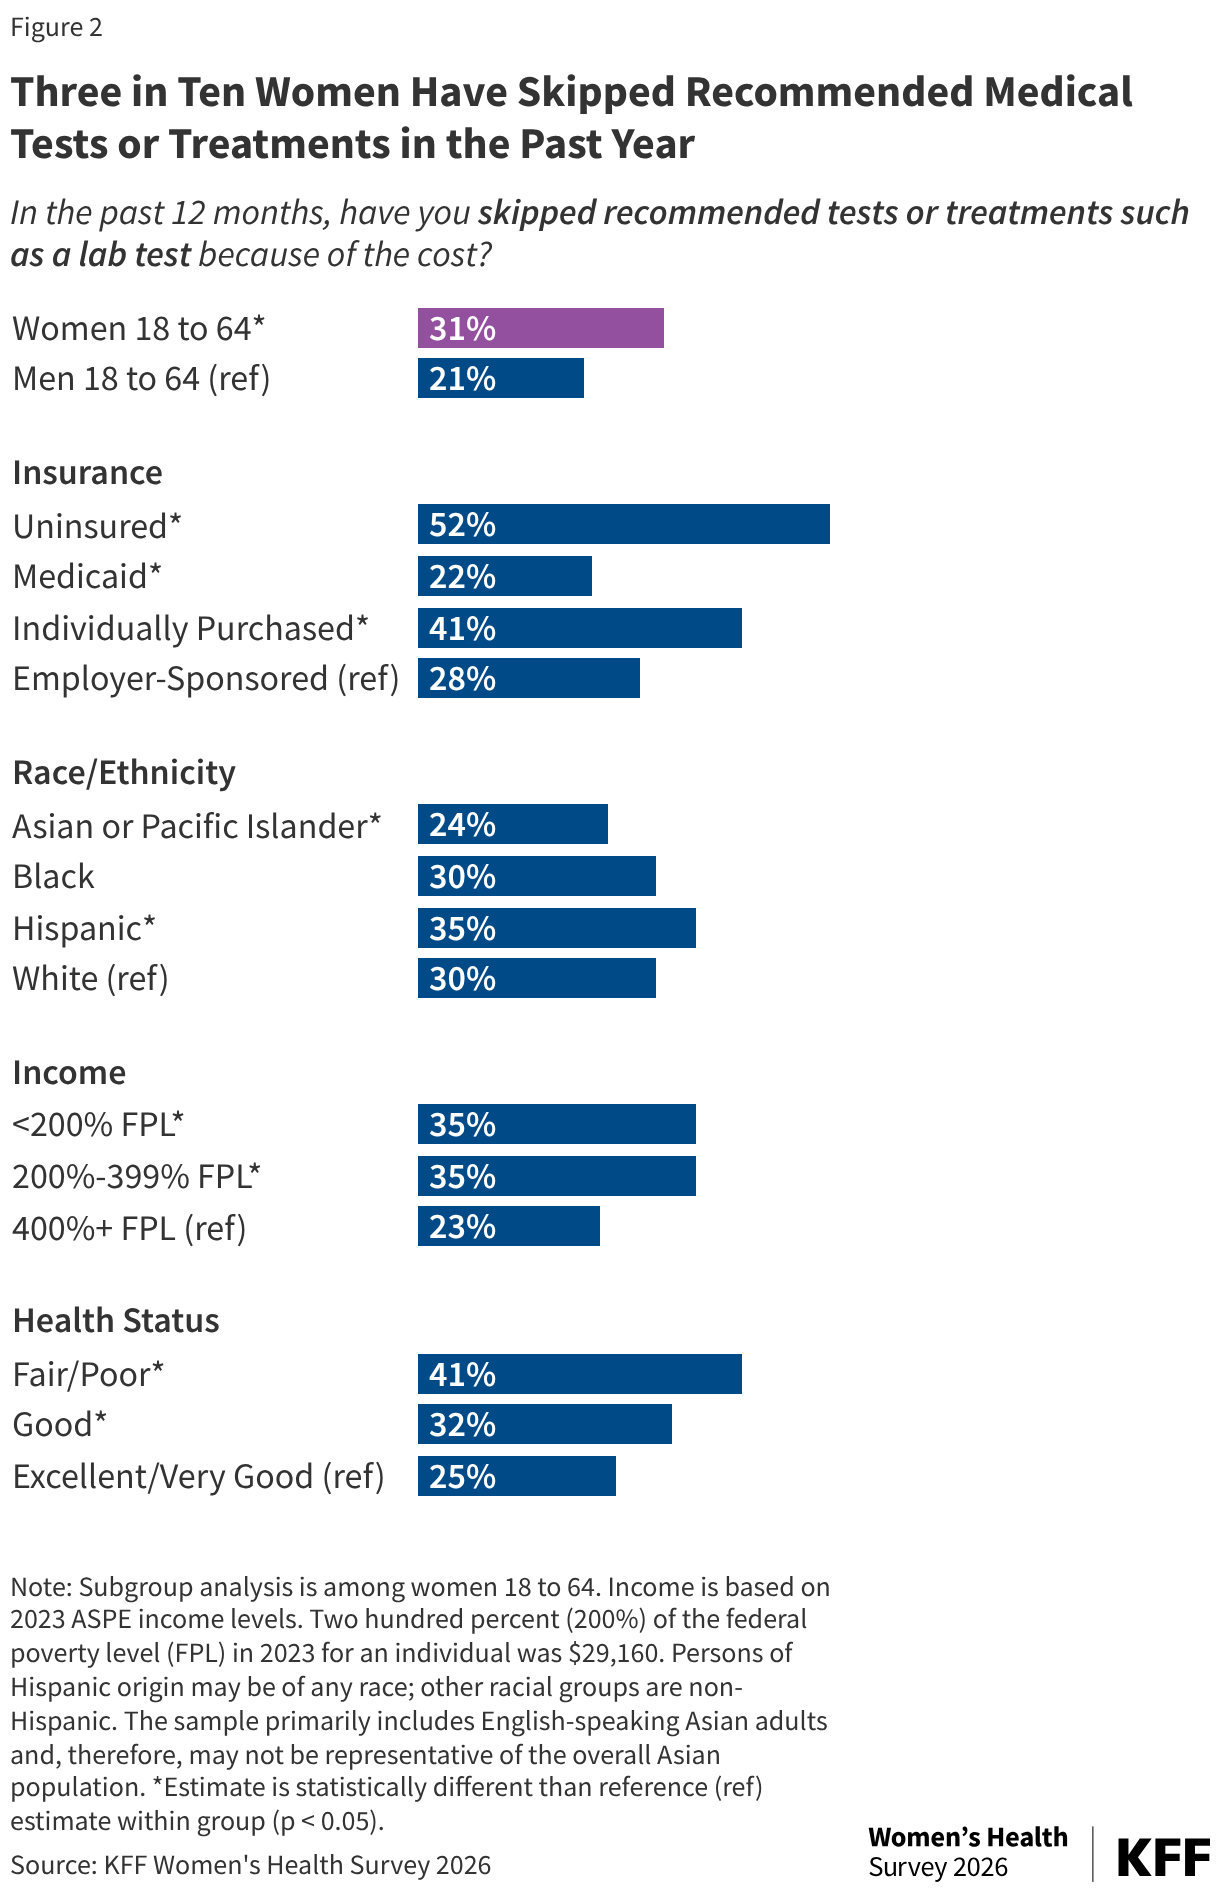
  • The cost of care is a barrier to a sizable minority of women in getting specific recommended tests and treatments. Three in ten (31%) women ages 18 to 64 report they have skipped or postponed recommended medical tests or treatments in the past year because of costs. Higher shares of uninsured women, women with low or modest incomes, and those with self-reported fair or poor health report skipping or postponing tests or treatments due to the costs of care.
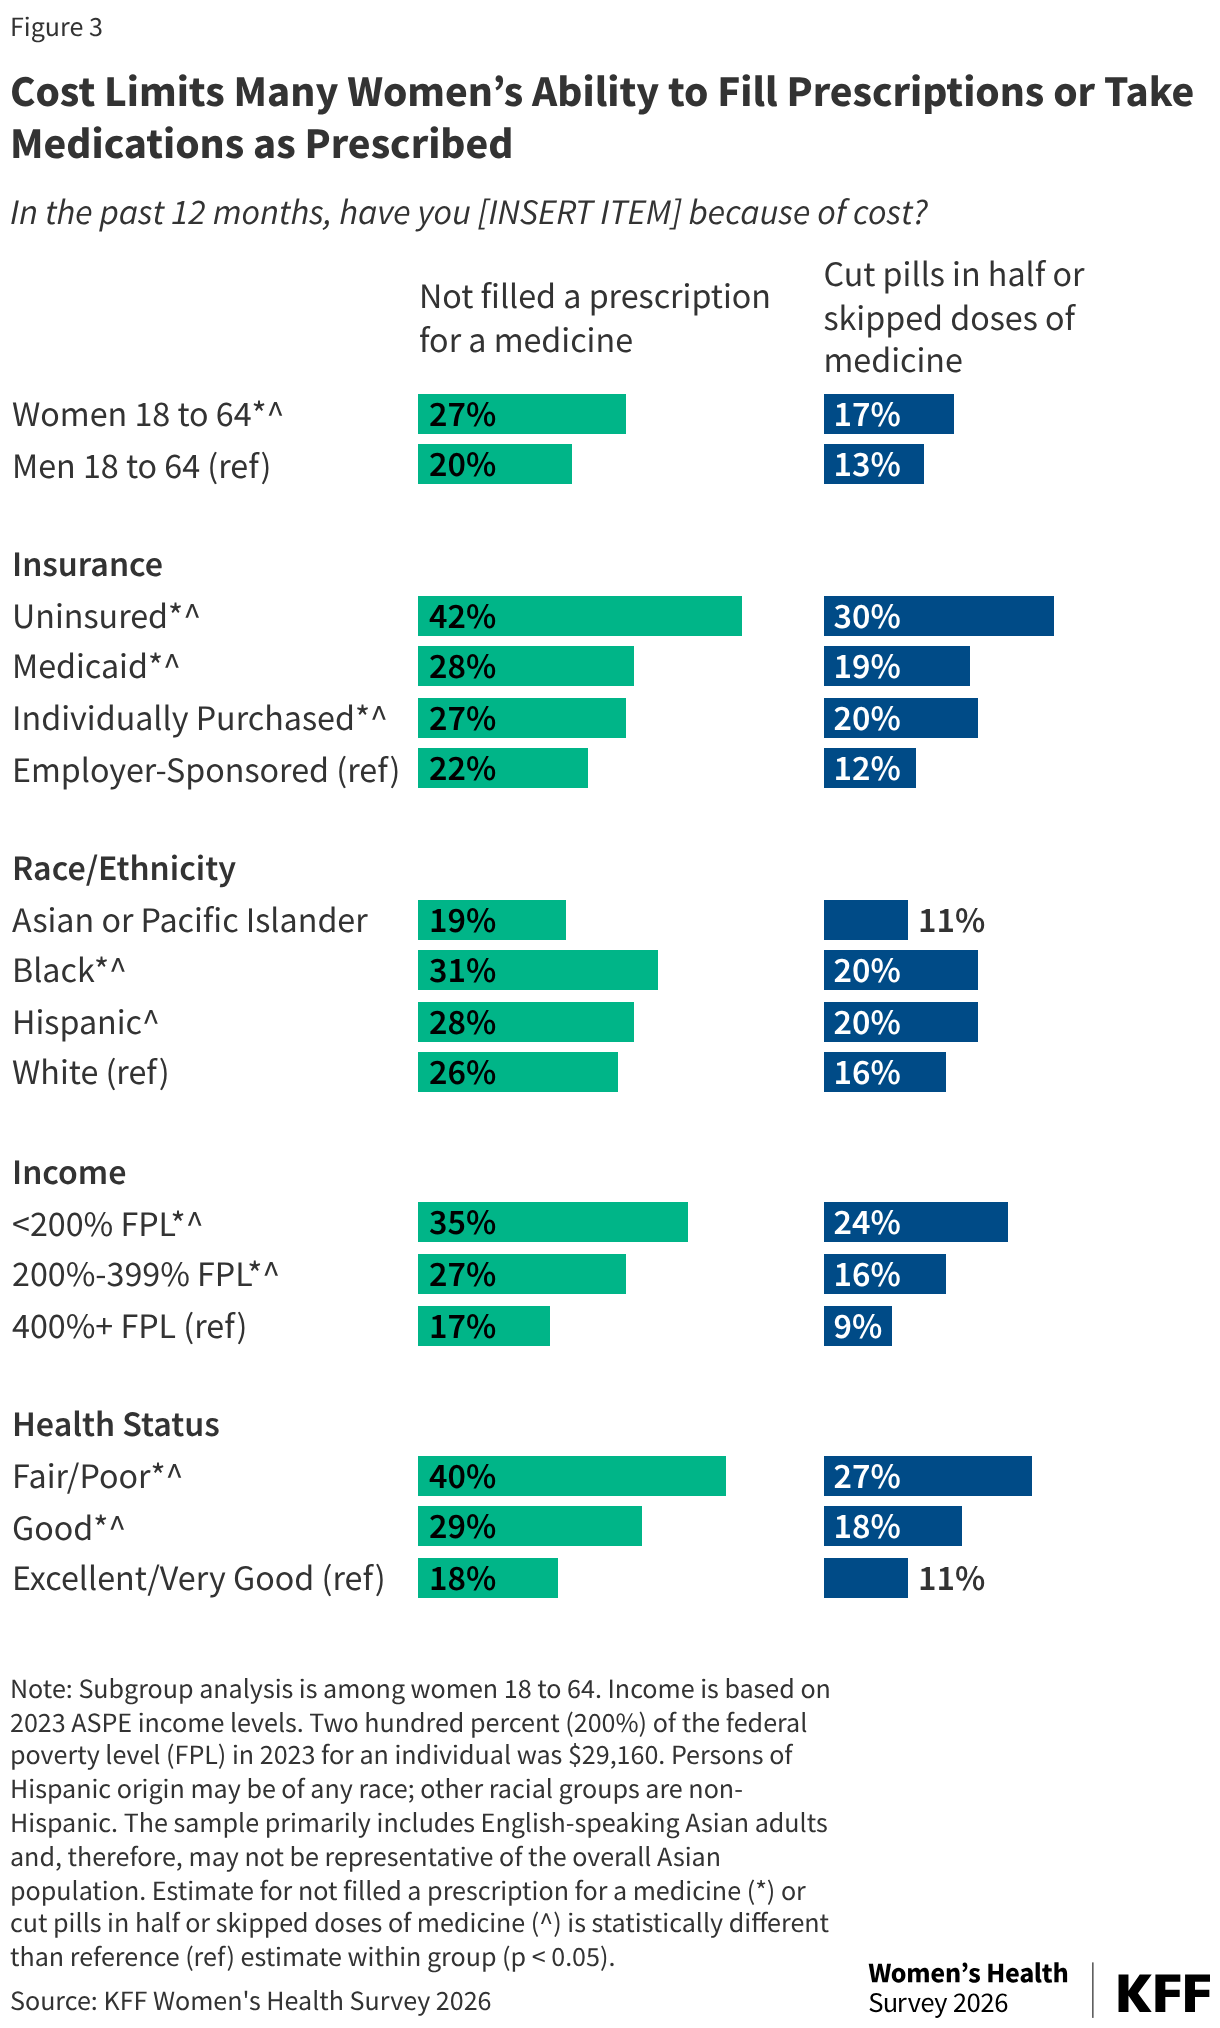
  • The cost of prescription drugs leads some women to alter their prescription drug use by not filling prescriptions, skipping doses, or cutting pills in half. A quarter (27%) of women ages 18 to 64 report they didn’t fill a prescription in the last year because of cost and almost a fifth (17%) report they cut pills in half or skipped doses of medicine because of cost. Four in ten women in fair or poor health didn’t fill prescriptions and one quarter cut pills or skipped doses because of costs.
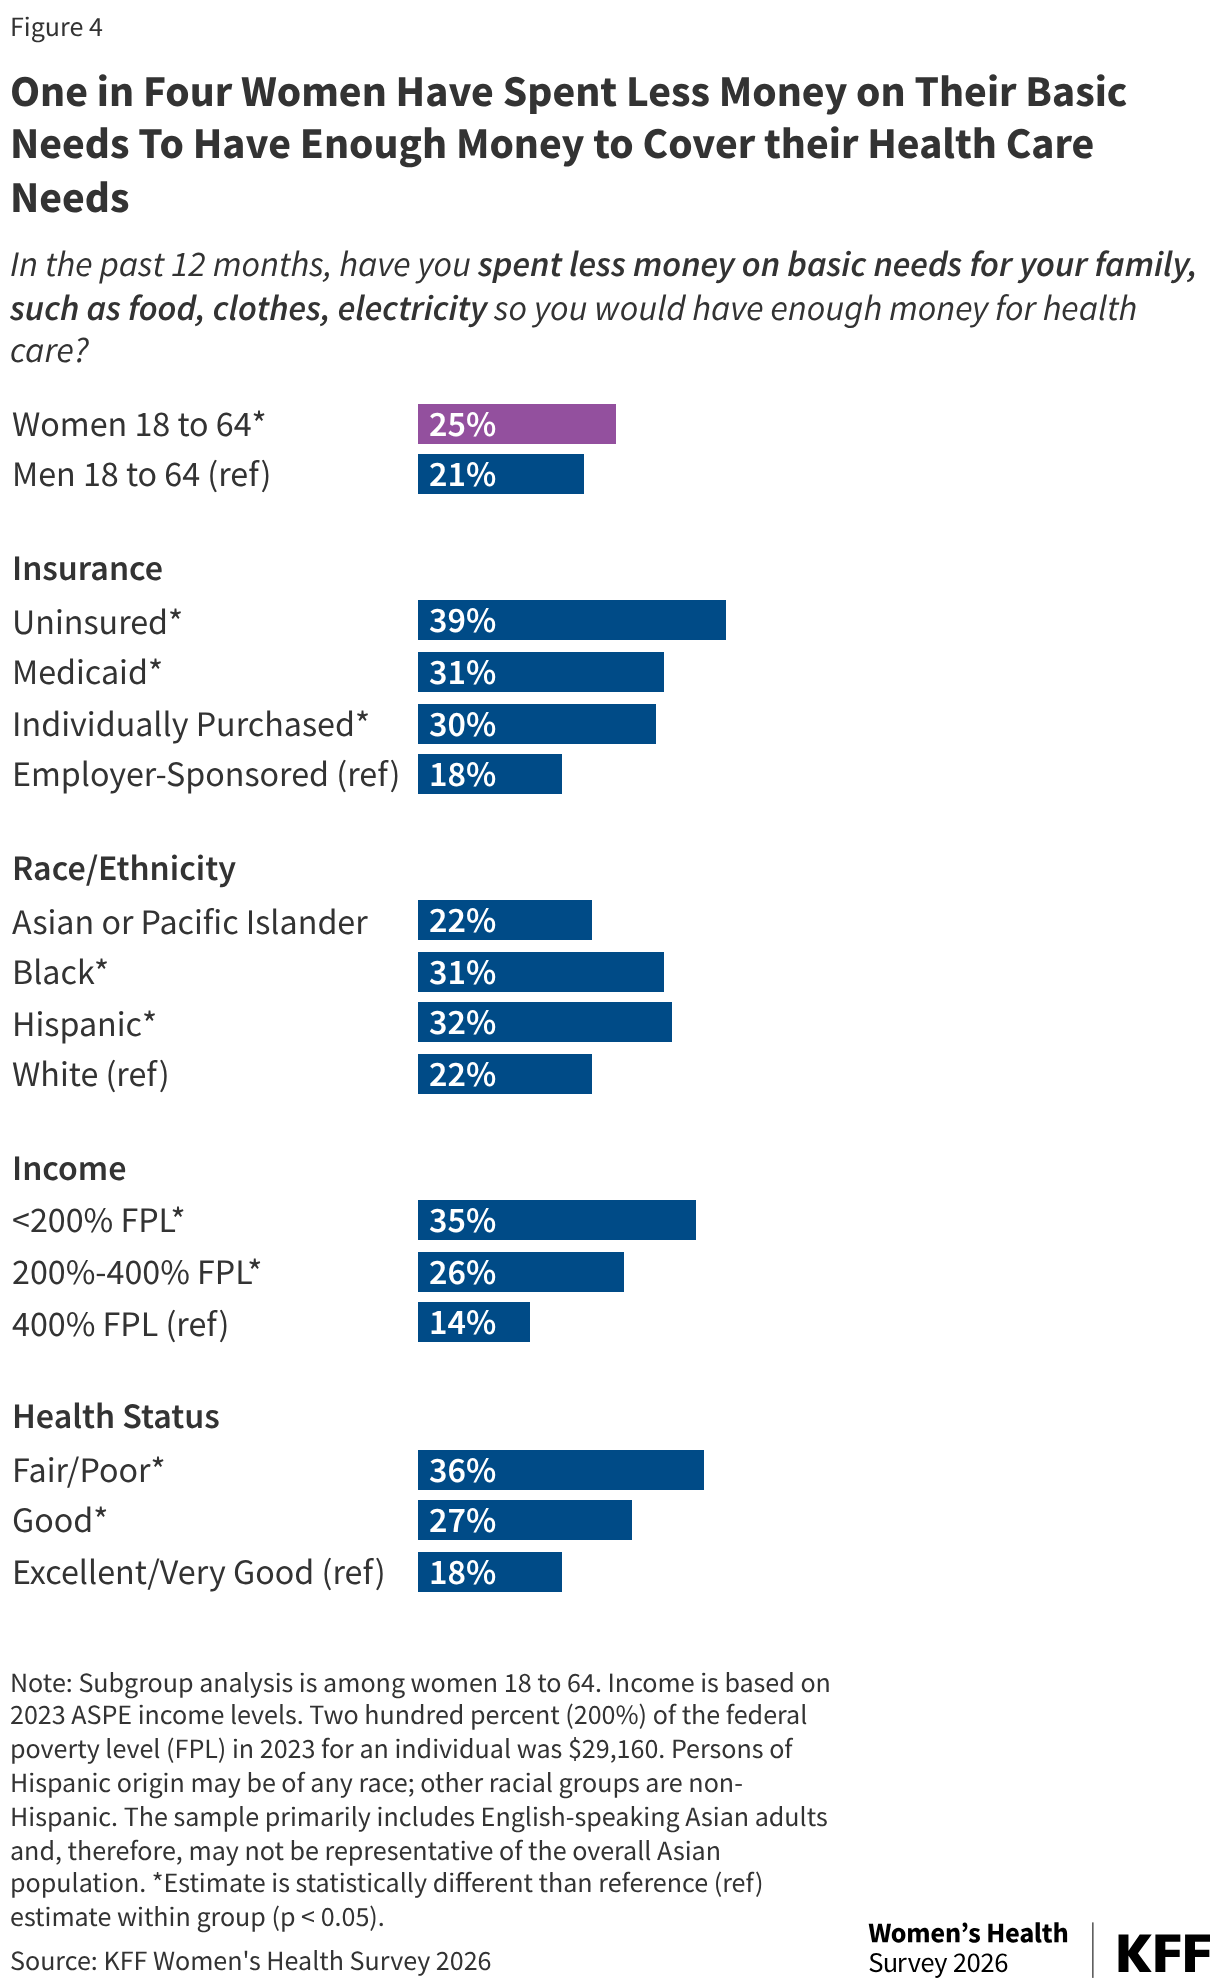
  • Health care costs can force some women to make tradeoffs in paying for other basic needs. One in four (25%) women ages 18 to 64 report that in the past 12 months they have spent less money on their basic needs, such as food, clothes and electricity so they could have enough money for health care. Among uninsured women, the share was 42%. Approximately three in ten women on Medicaid or with individually purchased insurance, who were Black or Hispanic, low-income or in fair or poor health report making health-related financial tradeoffs.

Affordability Challenges

Four in ten (42%) women report that they delayed or postponed care they thought they needed because of the cost in the last 12 months. While women and men both can feel the impact of health costs, such as insurance premiums, co-payments, and deductibles, they can be particularly burdensome for women who on average earn lower wages, have fewer financial assets, accumulate less wealth, and have higher rates of poverty than men. Four in ten (42%) women and 35% of men ages 18 to 64 report they have delayed or postponed care they thought they needed. One in three women (31%) report they have skipped recommended tests or treatments, over a quarter (27%) report they haven’t filled a prescription for a medicine, and 17% report they have cut pills in half or skipped recommended doses of medicine, all because of cost. Half of women and four in ten (42%) men report one of these cost delays or gaps in the past 12 months.

Many women, even those with insurance coverage, report having delayed or postponed care because of cost. Nearly seven in 10 (68%) uninsured women say theydelayed or postponed care in the past 12 months because of the cost. While younger adults, those with lower incomes, poor health and people of color have higher uninsured rates, even after controlling for these characteristics in a regression model, the association between being uninsured and delaying or postponing care remains. Even women with insurance are susceptible to cost barriers (Figure 1). Half of women ages 18 to 64 with individually purchased plans, which often have higher deductibles and premiums as well as narrower networks, report cost was a reason for delaying or postponing care in the past 12 months, as do 38% of women with employer sponsored plans. Medicaid, the national health coverage program for people with low incomes, is supposed to have only nominal out of pocket costs, but a third (34%) of women with Medicaid coverage also say they had to delay or postpone care due to costs. While Medicaid copayments are modest, they could still be a financial burden for low-income people. Women could also face challenges paying for uncovered services or services during a period when they were uninsured. Women with lower incomes, Hispanic women, and women with fair/poor and good health are also more likely to report having delayed or postponed care in the past year.

Bar chart showing the share of women ages 18–64 who delayed or postponed needed care in the past 12 months because of cost, overall and by insurance, race/ethnicity, income, and health status. Forty-two percent of women delayed care, compared with 32% of men. Delayed care was highest among uninsured women (68%), women with fair or poor health (56%), and women with incomes below 200% of the federal poverty level (48%).

High costs can cause many women to skip specific recommended tests and treatments, even women with health coverage. Half (52%) of uninsured women ages 18 to 64 report skipping recommended tests or treatments due to cost, as do four in ten (41%) of women with individually purchased health plans, three in 10 (28%) women with employer sponsored plans, and one in five (22%) of women with Medicaid coverage (Figure 2). Higher shares of women with self-reported fair/poor health (40%) or good health (32%) report skipping recommended tests or treatments in the past year compared to a quarter of women (23%) who rate their health as excellent/ very good. Hispanic women and women with low or modest incomes (up to 399% FPL) are also more likely to report skipping recommended services compared to their White and higher income counterparts.

Bar chart showing the share of women who skipped recommended medical tests or treatments because of cost. Overall, 31% skipped care, with higher rates among uninsured women (52%), women with individually purchased coverage (41%), Hispanic women (35%), women with incomes below 400% of the FPL (35%), and women in fair or poor health (41%).

Cost limits women’s ability to fill their prescriptions or take their medications as prescribed. The majority of women ages 18 to 64 (62%) report they take at least one prescription medication on a regular basis, yet many women report issues affording prescription drugs. A quarter (27%) of all women ages 18-64, report they didn’t fill a prescription in the last year and almost a fifth (17%) report they cut pills in half or skipped doses of medicine because of cost. Among the share who report currently taking a prescription medication, the share who say they have not filled a prescription increases to 32% and one in five say they have cut pills in half or skipped doses in the past year because of cost.

Women with self-reported fair/poor and good health and women with lower incomes are more likely to report they have either not filled a prescription or taken medications as prescribed. A higher share of uninsured women report not filling a prescription (42%) or taking medication as prescribed (17%), but substantial shares of insured women also report having trouble with their prescriptions because of cost in the past 12 months (Figure 3).

Bar chart showing the share of women ages 18 to 64 who skipped filling a prescription or cut pills/skipped doses in the past 12 months because of cost, broken down by insurance, race/ethnicity, income, and health status. Cost-related barriers are highest among uninsured women, those with lower incomes, and those in fair or poor health, while women with employer-sponsored insurance, higher incomes, and better health report the lowest rates.

Health care costs can force women to make tradeoffs in paying for other basic needs. One in four (25%) women ages 18 to 64 report that in the past 12 months they have spent less money on their basic needs, such as food, clothes and electricity so they could have enough money for health care (Figure 4). Four in ten (39%) women without insurance and three in ten women with Medicaid (31%) coverage and individually purchased coverage (30%) report spending less in their basic needs to have enough money for health care compared to one in five (18%) women with employer-sponsored plans. This is more common amongwomen with lower incomes, Black and Hispanic women, as well as women with poorer self-reported health status.

Bar chart showing the share of women ages 18 to 64 who spent less on basic needs like food, clothes, or electricity in the past 12 months so they'd have enough money for health care, broken down by insurance, race/ethnicity, income, and health status. About one in four women overall report doing this, with the share notably higher among uninsured women, Black and Hispanic women, those with lower incomes, and those in fair or poor health.

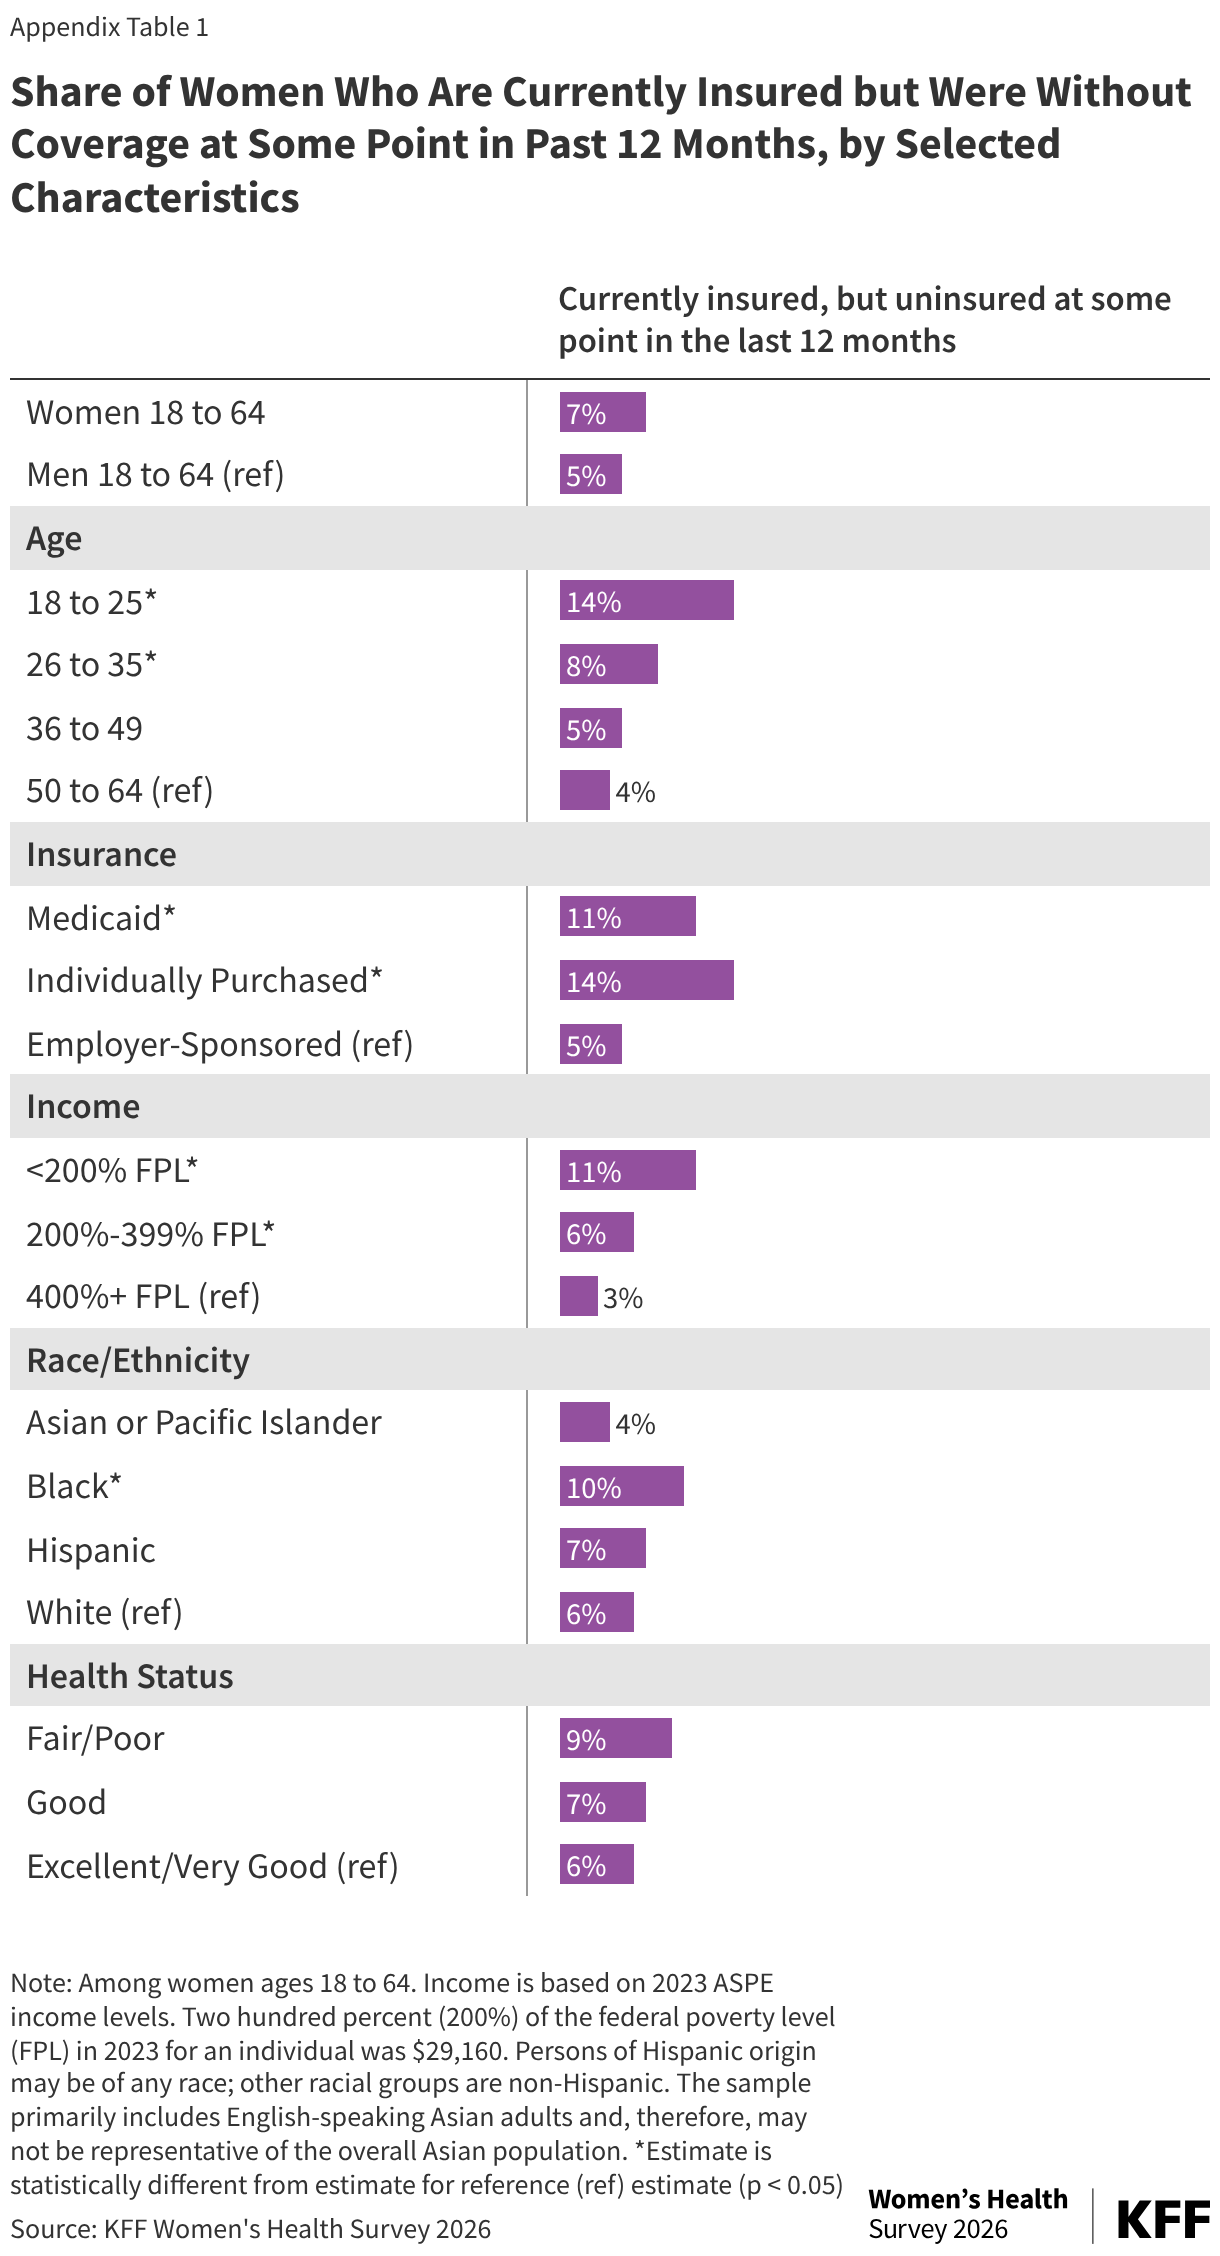
The majority of women 18 to 64 report they are insured, but almost one in five women 18 to 64 (18%) report they are either currently uninsured or were uninsured at some point in the past 12 months. Health insurance coverage is an important factor in making health care affordable and accessible to women.Seven percent of women say they are currently insured but were uninsured at some point during the past 12 months. Women can be uninsured for periods of time because of job loss or change, premium prices becoming unaffordable, or in the case of dependent coverage, a spouse’s job loss, divorce, or widowhood. Younger women, women with lower incomes and women with poor/fair health are uninsured at higher rates and larger shares report being currently insured but having been uninsured at some point during the year (Appendix Table 1).

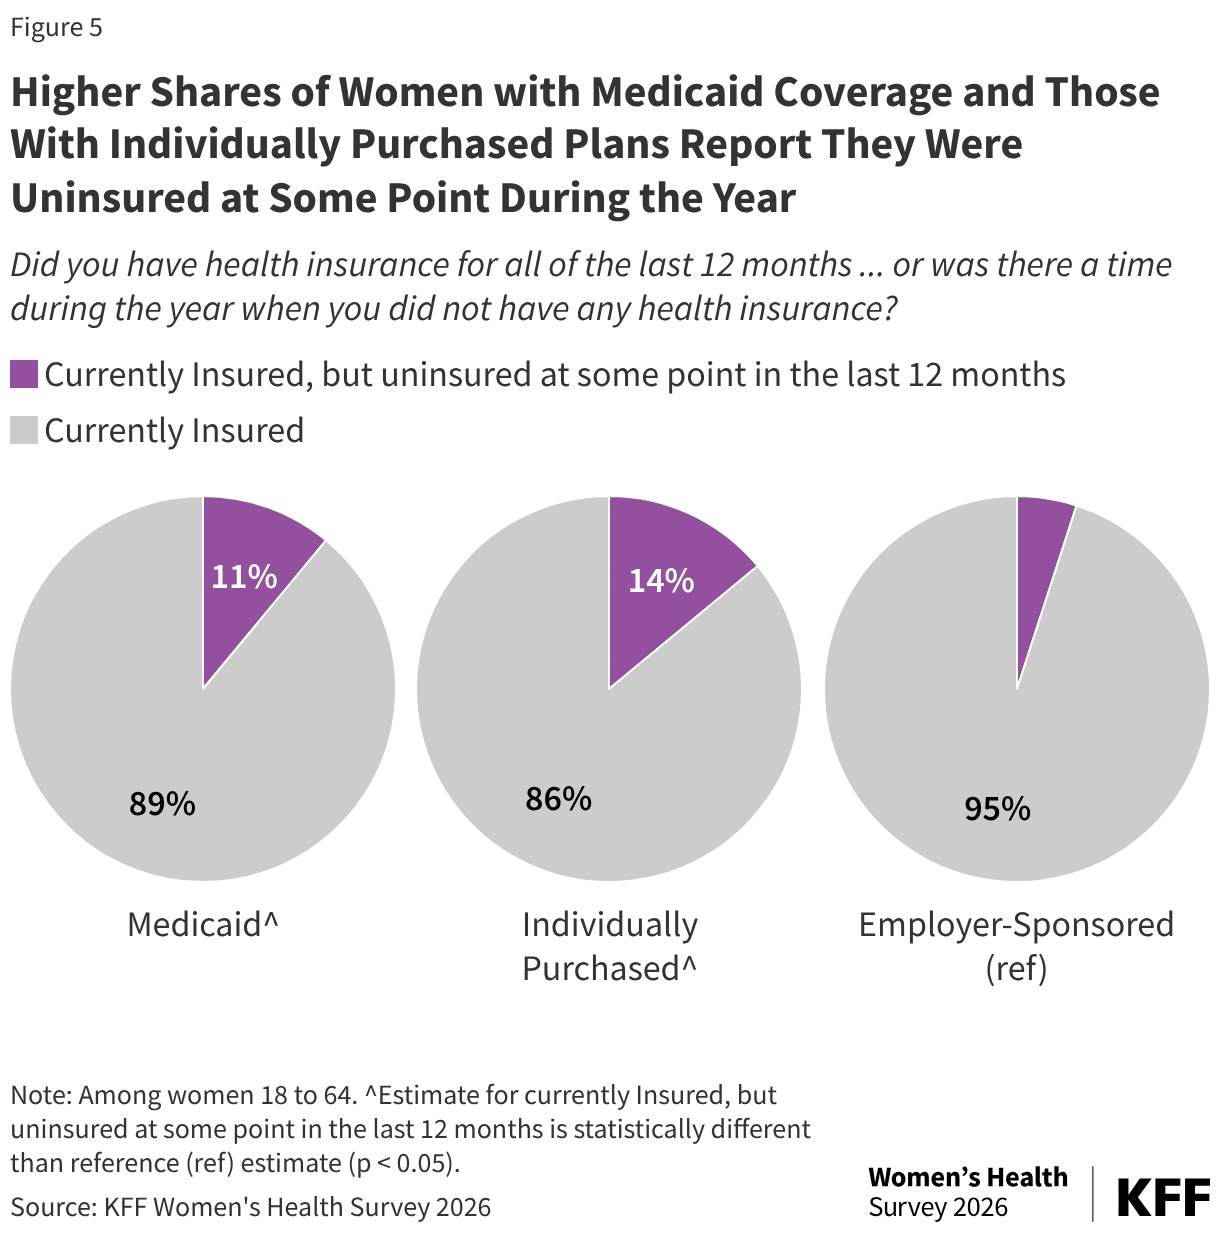
Women with Medicaid coverage (11%) and those with individually purchased private plans (14%) are more likely to report having been uninsured at some point in the past 12 months compared to women covered by an employer-sponsored plan (5%) (Figure 5). In the coming years, the number of uninsured is expected to increase significantly due to recent federal policy changes in Medicaid and the expiration of the ACA enhanced tax credits. Many women with Medicaid coverage and ACA marketplace plans will be directly impacted by these policy changes and will likely see more periods without insurance coverage.

Three pie charts showing the share of women ages 18 to 64 who are currently insured but were uninsured at some point in the past 12 months, broken out by current insurance type. Women with Medicaid or individually purchased plans are notably more likely to have had a coverage gap during the year than those with employer-sponsored insurance.
Bar chart showing the share of currently insured women ages 18 to 64 who were without coverage at some point in the past 12 months, broken down by age, insurance type, income, race/ethnicity, and health status. Younger women and those with Medicaid, individually purchased plans, or lower incomes report the highest rates of a coverage gap during the year.

The 2026 KFF Women’s Health Survey was designed and analyzed by women’s health researchers at KFF. The survey was conducted from March 11 – April 14, 2026, online and by telephone among a nationally representative sample of 5,854 adults ages 18 to 64, including 3,538 women ages 18 to 49. Women include anyone who selected woman as their gender. Sampling, data collection, weighting, tabulation, and IRB approval by the University of Southern Maine’s Collaborative Institutional Review Board were managed by SSRS of Glenn Mills, Pennsylvania in collaboration with women’s health researchers at KFF.

Throughout the reports of findings, we refer to “women.” This includes respondents who said their gender is “woman,” and includes those who selected “woman” in addition to another gender, such as “transgender,” or “non-binary,” or another gender. We followed this approach to try to include as many people as possible but recognize that some people who need and seek abortion and other reproductive health care services may not be represented in the findings or identify as women. Some questions about sexual and reproductive health were only asked among those with a specific sex assigned at birth (i.e. male or female).

The national sample was drawn from two nationally representative probability-based panels: the SSRS Opinion Panel and the Ipsos Knowledge-Panel. The SSRS Opinion Panel is a nationally representative probability-based panel where panel members are recruited randomly in one of two ways: (a) Through invitations mailed to respondents randomly sampled from an Address-Based Sample (ABS) provided by Marketing Systems Groups (MSG) through the U.S. Postal Service’s Computerized Delivery Sequence (CDS); (b) from a dual-frame random digit dial (RDD) sample provided by MSG. For the online panel component, invitations were sent to panel members by email followed by up to five reminder emails. 5,660 panel members completed the survey online and panel members who do not use the internet were reached by phone (n=194). Another 514 respondents were reached online through the Ipsos Knowledge Panel to help reach adequate sample sizes among subgroups of interest, specifically women ages 18 to 49. This panel is recruited using ABS, based on a stratified sample from the CDS. The questionnaire was translated into Spanish, so respondents were able to complete the survey in English or Spanish. 

The national sample was weighted by splitting the sample into three groups: [1] Women 18-49, [2] Women 50-64, and [3] Men 18-64 and each group was separately weighted to match known population parameters (see table below for weighting variables and sources). Weights within the three groups were then trimmed at the 4th and 96th percentiles, to ensure that individual respondents do not have too much influence on survey-derived estimates. After the weights were trimmed, the samples were combined, and the weights adjusted, so that the groups were represented in their proper proportions for a final combined, gender by age-adjusted weight.

DimensionsSource
CPS 2024 Voting and Registration SupplementCurrent Population Survey 2025
Education
Age by Education
Age by Gender
Census Region
Race/Ethnicity by Nativity
Home Tenure
Civic Engagement2023 CPS Volunteering and Civic Life Supplement
Internet FrequencyPew Research Center’s National Public Opinion Reference Survey (NPORS 2025)
Population DensityClaritas Pop-Facts Premier 2026
Voter RegistrationCPS 2024 Voting and Registration Supplement

The margins of sampling error for the national sample of women ages 18 to 64 and reproductive age women ages 18 to 49 are plus or minus 2 percentage points. Numbers of respondents and margins of sampling error for key subgroups are shown in the table below. For results based on other subgroups, the margin of sampling error may be higher. Sampling error is only one of many potential sources of error and there may be other unmeasured error in this survey.

GroupN (unweighted)M.O.S.E.
National Women Ages 18-644,688± 2 percentage points
White, non-Hispanic2,262± 2 percentage points
Black, non-Hispanic767± 4 percentage points
Hispanic1,135± 4 percentage points
Asian or Pacific Islander347± 6 percentage points
18-25508± 5 percentage points
26-351,313± 3 percentage points
36-491,715± 3 percentage points
50-641,152± 3 percentage points
<200% FPL1,641± 3 percentage points
200%-399% FPL1,232± 3 percentage points
400%+ FPL1,475± 3 percentage points
Employer-Sponsored2,490± 2 percentage points
Individually Purchased386±6 percentage points
Medicaid977± 4 percentage points
Uninsured537± 5 percentage points

General Notes:

The sample primarily includes English-speaking Asian adults and, therefore, may not be representative of the overall Asian adult population. Despite this limitation, it is important to report the views of Asian adults on the topics in this study. As always, Asian adults’ responses are incorporated into the general population figures throughout this report.

Income is based on 2023 ASPE income levels. Two hundred percent (200%) of the federal poverty level (FPL) in 2023 for an individual was $29,160.

Endnote

  1. The data in this brief report affordability challenges for adults ages 18 to 64. Other KFF polling data includes estimates for all adult women and men, including those 65 and older. ↩︎
Poll Finding

KFF/AP Rural Voters Survey

Published: Sep 23, 2026

This KFF/AP Rural Voters Survey was designed and analyzed by public opinion researchers at KFF and The Associated Press. The survey was conducted online and by telephone August 12-24, 2026 among a nationally representative sample of 2,241 U.S. adults registered to vote in rural areas of the country. KFF and the AP each contributed financing for the survey, and representatives of each organization worked together to develop the survey questionnaire and analyze the results. Each organization bears the sole responsibility for the work that appears under its name. Sampling, data collection, weighting, and tabulation were managed by SSRS in close collaboration with KFF.

Interviews were administered in English (n=2,236) and Spanish (n=5) combining samples from the SSRS Opinion Panel who have been matched to the L2 voter file. and a stratified Registration-Based Sample (RBS) from the L2 voter file. For this study, rural areas were defined as those in Census tracts that fall within codes 5-10 of the USDA’s 2020 Rural-Urban Commuting Area (RUCA) Codes.

1,577 registered voters living in rural areas were reached through the SSRS Opinion Panel, The SSRS Opinion Panel is a nationally representative probability-based panel where panel members are recruited randomly in one of two ways: (a) Through invitations mailed to respondents randomly sampled from an Address-Based Sample (ABS) provided by Marketing Systems Groups (MSG) through the U.S. Postal Service’s Computerized Delivery Sequence (CDS); (b) from a dual-frame random digit dial (RDD) sample provided by MSG. For the online panel component, invitations were sent to panel members by email followed by up to three reminder emails. Telephone panelists received up to four phone calls.

Another 664 rural adults were reached through a stratified Registration-Based Sample (RBS) from the L2 voter file. Stratification was based on rurality, race, and geography. RBS cases were invited to the survey through multiple contacts: An invitation letter including non-contingent incentive and a follow-up postcard to all, email reminders to those with a listed email address, text-message reminders to those with a cell phone number matched to the voter file, and outbound telephone calls to those with phone number matched to the voter file.

Individuals who completed the survey received a monetary incentive for their participation including either a $10 electronic gift card or a $10 incentive check depending on the method of contact. In order to ensure data quality, cases were removed if they failed two or more quality checks: (1) attention check questions in the online version of the questionnaire, (2) had over 30% item non-response, or (3) had a length less than one quarter of the mean length by mode. Based on this criterion, eight cases were removed.

A multi-stage weighting process was applied to ensure an accurate representation of the population including adjustments for the sample design and within household probability of selection. The combined panel and RBS samples were weighted to match the sample’s demographics to the U.S. rural registered voter population using data from the L2 voter file. The variables included in weighting are gender, age, education level, race and ethnicity, Census region, RUCA category, 2024 turnout, and modeled likely 2024 vote choice.  

The margin of sampling error including the design effect for the full sample is plus or minus 3 percentage points. Numbers of respondents and margins of sampling error for key subgroups are shown in the table below. For results based on other subgroups, the margin of sampling error may be higher. Sample sizes and margins of sampling error for other subgroups are available on request. Sampling error is only one of many potential sources of error and there may be other unmeasured error in this or any other public opinion poll. KFF public opinion and survey research is a charter member of the Transparency Initiative of the American Association for Public Opinion Research.

GroupN (unweighted)M.O.S.E.
Total2,241± 3 percentage points
Party/Party Lean
Democrat/Lean Democrat836± 4 percentage points
Republican/Lean Republican1,174± 4 percentage points
Pure Independent177± 9 percentage points
 
MAGA Republicans/Rep leaners883± 4 percentage points
NOT MAGA Republicans/Rep leaners288± 7 percentage points

Key Takeaways

  • Economic frustrations in rural America have significantly worsened over the past decade, and growing dissatisfaction with the rising cost of living appears to be chipping away at rural voters’ historical support for President Trump. Rural voters overwhelmingly name the cost of living as their top election issue, and three quarters, including majorities across partisanship, now rate the cost of living in their area as either “fair” or “poor,” a 25-percentage point increase from 2017. While more rural voters prefer the Republican Party than the Democrats to best address the cost of living (40% v. 25%), many (27%) say they trust neither party, including most independents (67%) and four in ten (42%) Republicans who do not support the MAGA movement.
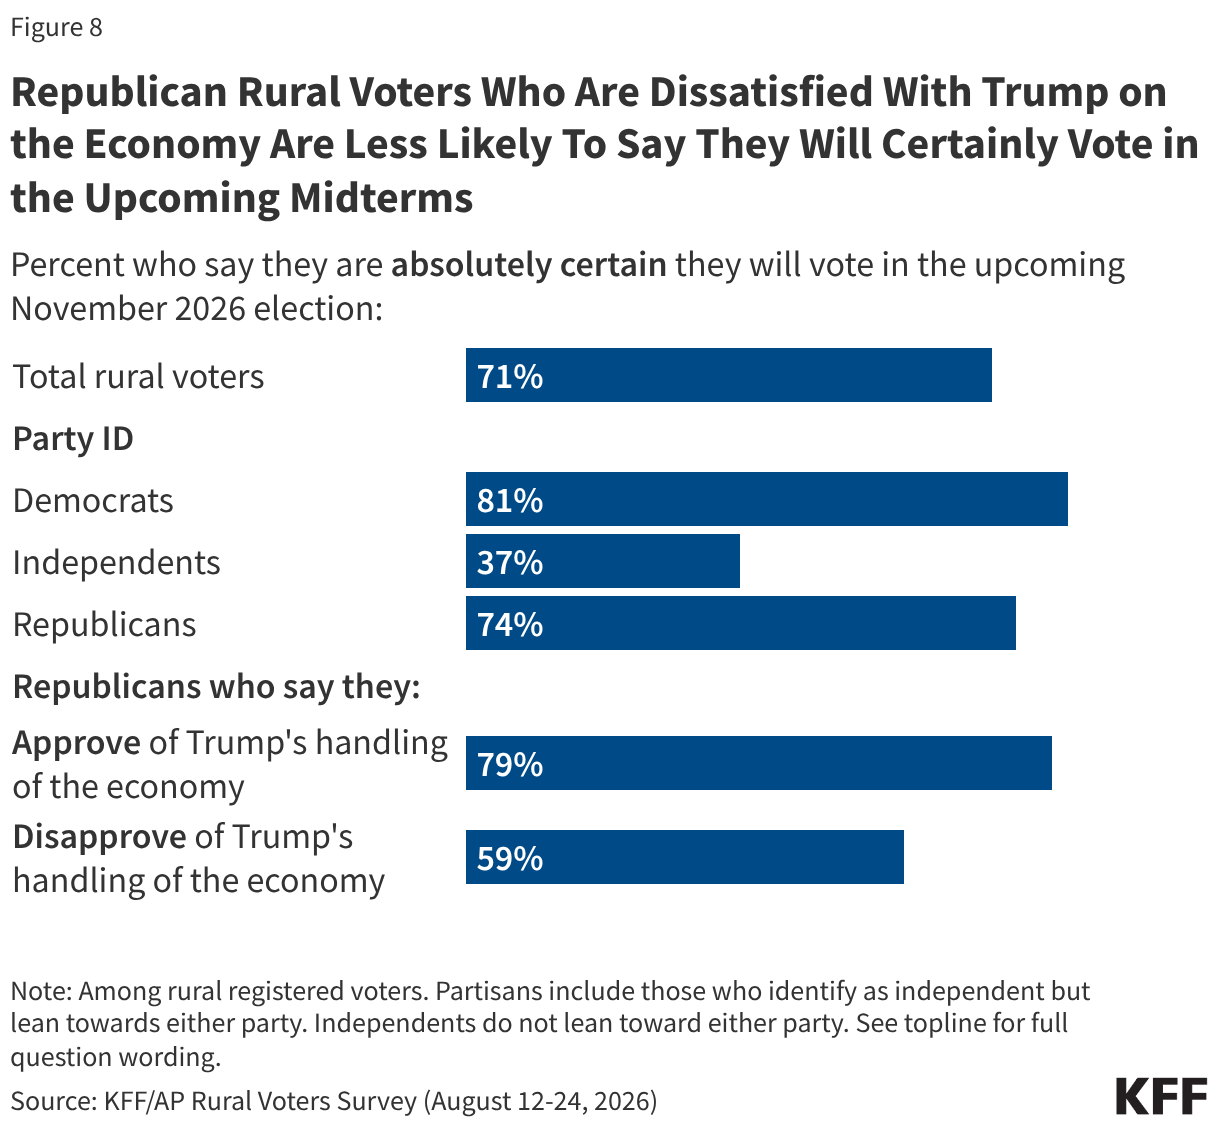
  • President Trump continues to garner strong approval among his base of Republicans across rural America, but growing economic frustrations may be impacting some Republicans’ enthusiasm to turn out in the 2026 midterms. About one-quarter (27%) of rural Republican voters disapprove of Trump’s handling of the economy, and this group is substantially less likely than Republicans who approve of Trump on the economy to say they are “absolutely certain” to vote in the upcoming election (59% vs. 79%). Overall, eight in ten Democratic rural voters (81%) say they are certain to vote, slightly higher than the share of Republican rural voters who say the same (74%).
  • As KFF polling has found nationally, health care costs play a large part in rural voters’ concerns about the cost of living. Two-thirds of rural voters say they are at least “somewhat worried” about affording health care for themselves or their families, on par with the share who say they are worried about affording gas (67%) and higher than worries about affording food (60%), monthly utilities (59%), or housing costs (46%).
  • More than half (54%) of rural voters disapprove of President Trump’s handling of health care, and views on the impact of his administration’s policies on areas like health care costs, Medicare, Medicaid, and the availability of health care are largely negative. For example, by more than a 2-to-1 margin, rural voters say the Trump administration’s policies have had a negative rather than a positive impact on their own health care costs (41% vs. 17%). Still, the Republican Party has a narrow advantage over the Democratic Party in rural voters’ trust to handle the cost of health care (33% vs. 28%), though about three in ten Republicans (28%) say they trust neither party on health care costs, rising to six in ten (59%) among independent rural voters. 
  • The overwhelming majority (92%) of rural voters say Medicaid is important for people in their local community and half have had a personal or family connection to the program at some point in their lives. However, awareness of future cuts to the program included in President Trump’s “One Big Beautiful Bill” is low among rural voters, with most saying they don’t know whether the legislation increases or decreases future federal spending on Medicaid. Despite this, nearly twice as many rural voters say Trump’s health care policies have had a negative rather than a positive impact on Medicaid (44% vs. 24%). While rural Republican voters are more likely to say the impact of Trump’s policies on Medicaid has been positive (40%), a similar share (43%) say they have had no impact.
  • Provider shortages have been a persistent challenge in rural areas, and the poll finds increases since 2017 in the share of rural voters saying their area lacks sufficient doctors (46%, up from 33%) and hospitals (35%, up from 21%) to serve the needs of the local community. Some voters appear to attribute responsibility to the Trump administration, with more than twice as many saying the administration’s policies have had a negative rather than a positive impact on the availability of health care in their area (37% vs. 15%).

Partisan Identification Among Rural Voters

The KFF/AP Rural Voters Survey draws from a nationally representative sample of 2,241 registered voters who currently live in census tracts classified as rural areas.

Rural voters skew more Republican compared to voters nationally, a difference that plays a role in their overall views and preferences on a range of issues.

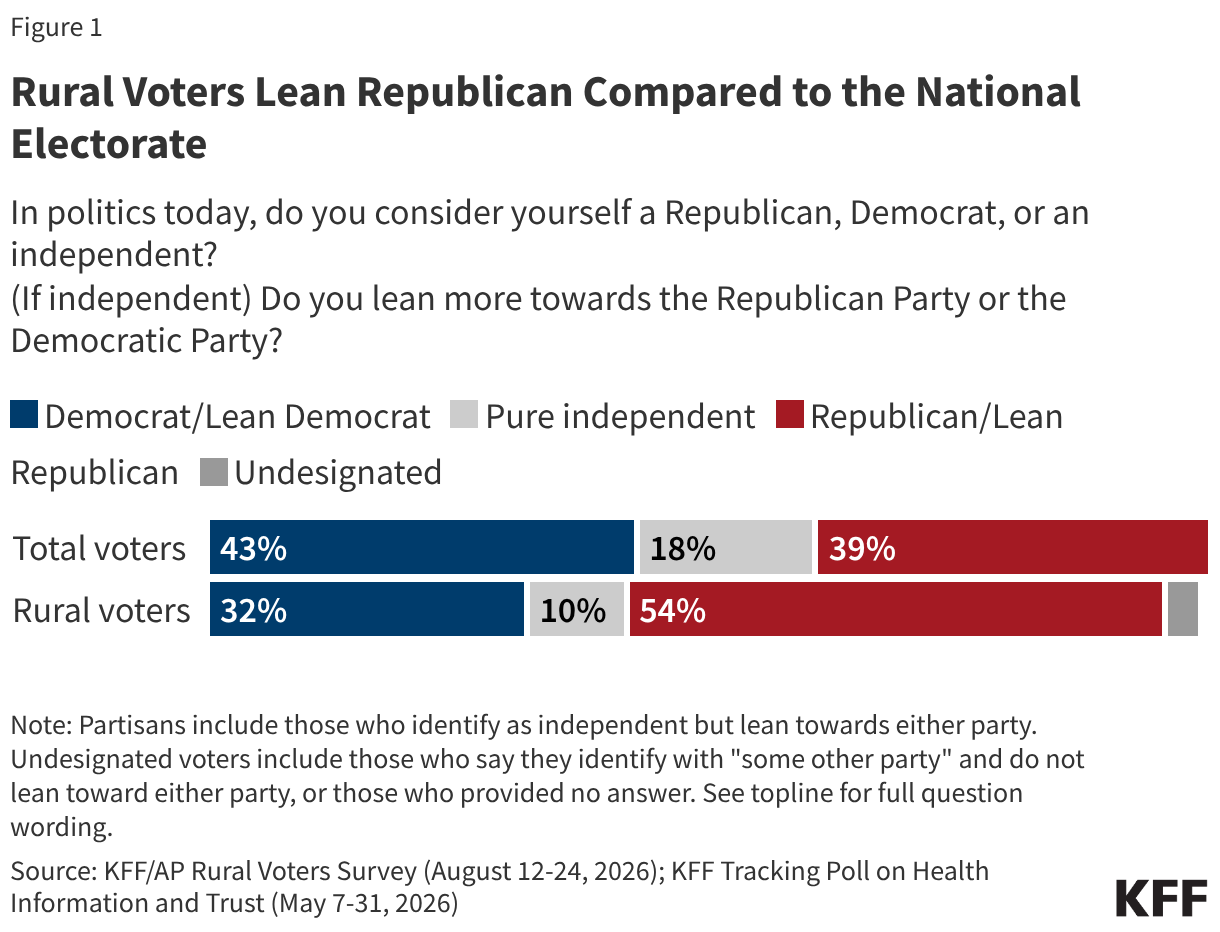
Slightly more than half (54%) of rural voters identify as Republicans or Republican-leaning independents versus one-third (32%) who are Democrats or Democratic-leaning independents. A previous KFF poll found the national electorate is more evenly divided, with roughly similar shares identifying as either Democratic/Democratic-leaning (43%) or Republican/Republican-leaning (39%).

In addition to partisanship, this report also breaks out Republican/Republican-leaning rural voters by their support for President Trump’s Make America Great Again (MAGA) movement. Three quarters of Republican rural voters say they support the MAGA movement, while a quarter (24%) do not.

Stacked bar chart showing the partisan breakdown of total voters and rural voters.

Cost of Living is the Top Issue for Rural Voters in 2026

A key theme echoed by majorities of rural voters across the country is that the current economic situation in the U.S. is putting significant pressure on them and their families – and it is what they want the candidates to be focused on during the 2026 election.

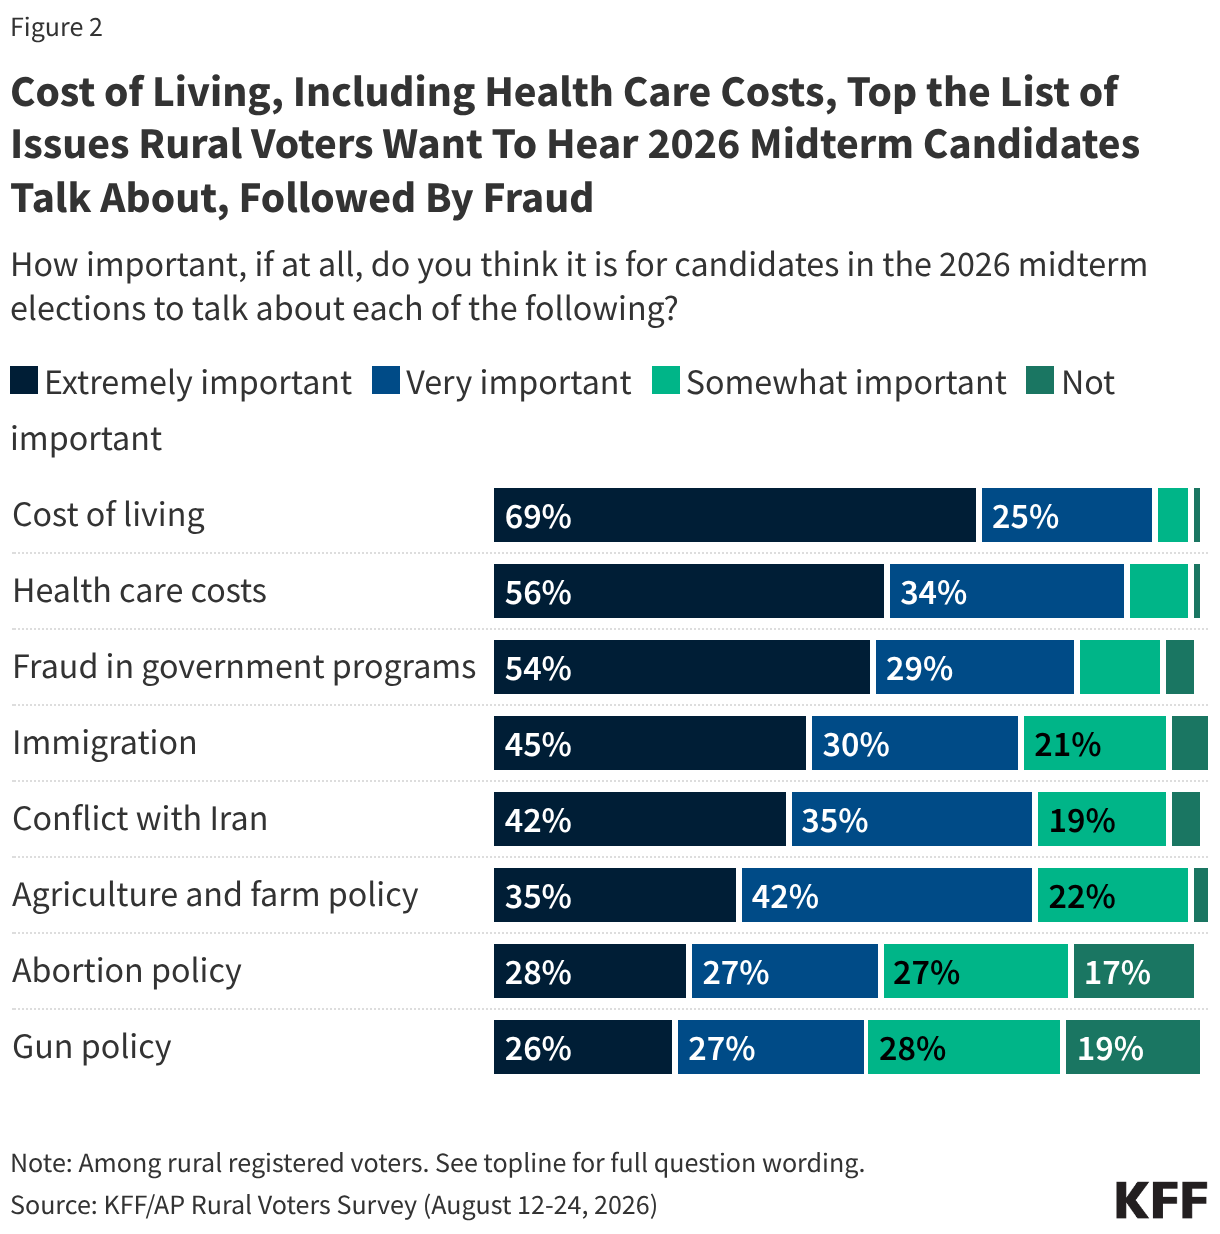
Cost of living is the top issue that rural voters want to hear midterm candidates talk about. About seven in ten (69%) rural voters say it is “extremely important” for candidates in the 2026 midterm elections to talk about cost of living, followed by health care costs (56%) and fraud in government programs (54%). Four in ten or more of these voters say it’s “extremely important” for candidates to talk about immigration (45%) or the conflict with Iran (42%), while smaller shares say they want to hear candidates talk about agriculture and farm policy (35%), abortion policy (28%), or gun policy (26%).

Stacked bar chart showing how important rural voters say certain issues are for midterm candidates to talk about.

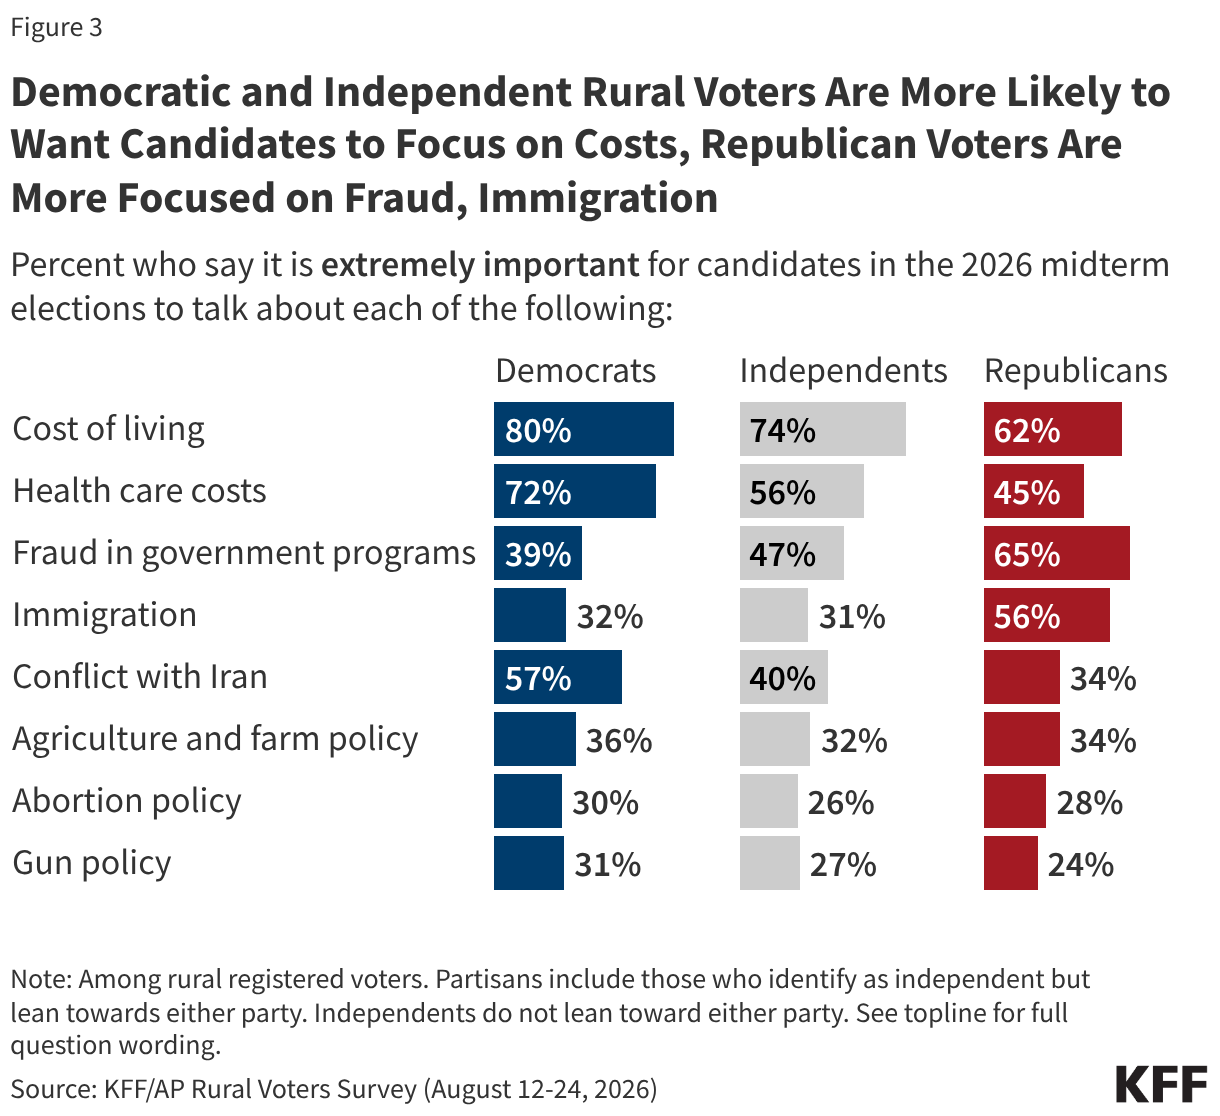
While cost of living is a top concern across partisans,1 the ranking of issues differs. The top three issues Republican rural voters want candidates to discuss are fraud in government programs (65%), cost of living (62%), and immigration (56%). For Democratic voters in rural areas, the top three concerns are cost of living (80%), health care costs (72%), and the conflict with Iran (57%).

Split bar chart showing the share of rural voter partisans who say it is extremely important for midterm candidates to talk about certain issues.

In addition, rural voters overwhelmingly name economic factors, especially the rising cost of living, as the biggest problem in their communities. When asked what the biggest issue facing their local community is, roughly six in ten (57%) of these voters offer responses related to economic concerns as their community’s biggest issue, including rising costs, lack of jobs, low wages, housing affordability, and stagnant local economies.

In Their Own Words: Rural Voters Describe the Biggest Economic Problems Facing Their Local Communities

“Everything is expensive, the price of living is horrendous. It is impossible to even think of raising a family in this current climate. You can't even sustain one single person with one form of income, when most places aren't hiring full time so you have to have 2-3 part time jobs to sustain yourself.” – 27-year-old rural voter from Alabama, Democratic-leaning independent

“I think prices are too high right now. Also, the government takes way, way too much in taxes, leaving people too little to live on. We have to live within our means and balance our finances …Almost all of the politicians are hypocrites.” – 66-year-old rural voter from Ohio, Republican

“Gas prices are financially impacting me in a major way, someone who has to drive 45 minutes, each way, to work because I live rural, is impacting my budget. Between the gas prices and food prices increasing, I pay over $300 more on my budget. That's not a little amount when every penny counts. Also, property taxes have doubled in the last 4 years.” – 51-year-old rural voter from Florida, independent who doesn’t lean toward either party

“Healthcare and our economy, no new jobs, inflation, gas prices, electricity, water supply is not clean, hard to save money when you’re paying it just to survive and support yourself and your children and grandchildren.” – 56-year-old rural voter from West Virginia, Democrat

“Electric bills and bills period. No one can afford to live anymore with the high food prices, high rent. Making do and I work 48 hrs a week with a family of 5 at home” – 36-year-old rural voter from New York, Republican

“We have lost several major manufacturing plants in my town. This resulted in a large portion of the community becoming unemployed. This has created a huge ripple effect of issues including a huge migration of people out of the area. Lower number of students enrolled has led to a drop in school funding and we are having to close an elementary school. The city council is proposing allowing a data center to be built close to town to "bring in jobs/opportunities" even though the majority of the community is against it and actively fighting it.” – 32-year-old rural voter from Kansas, Democrat

“The amount I am paying for groceries is too high for the income I make, and I am a teacher. I have a degree I should be able to afford a vacation for my family. I should be able to go to the local store and not pay about double what it is at Walmart.” – 26-year-old rural voter from North Dakota, Republican

Note: Responses are lightly edited for length and spelling, but reflect respondents' own language and do not represent the views of KFF.

Current Economic Conditions Weigh Heavily on Rural Voters

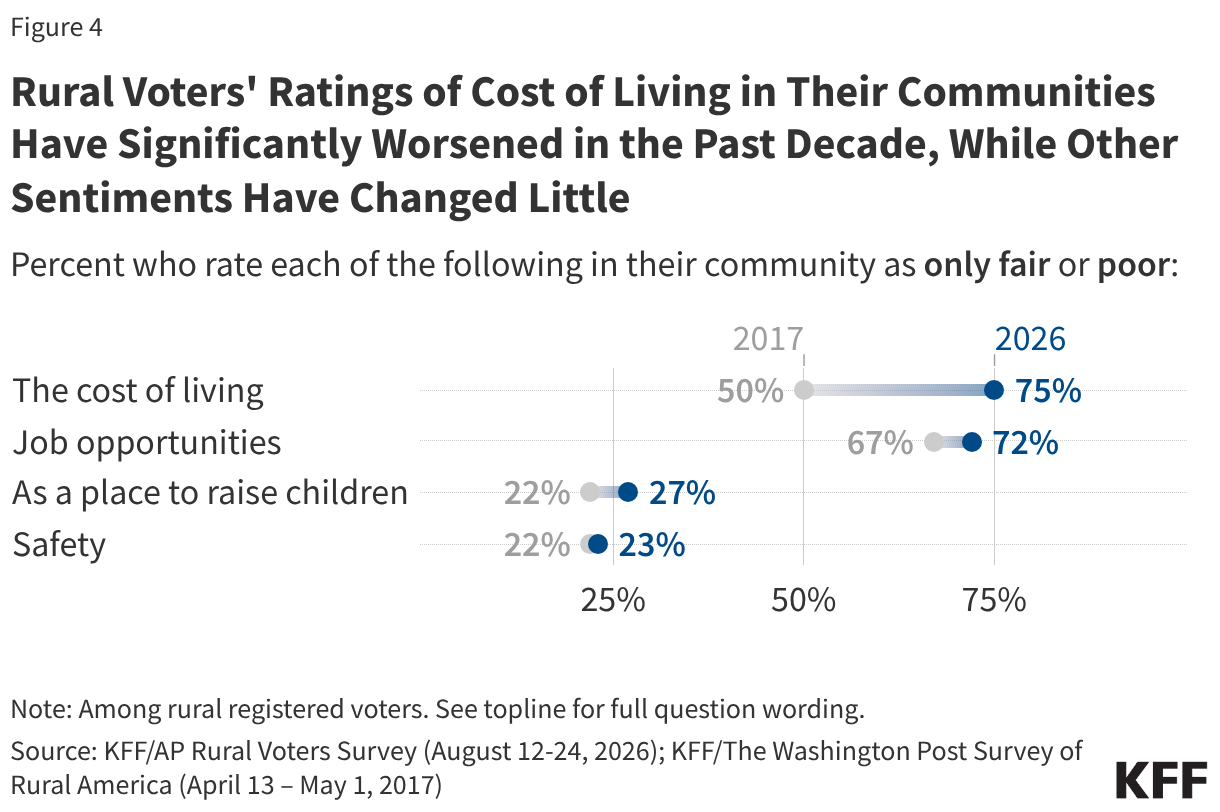
While most rural voters continue to have positive views of their community in terms of safety and raising children, their views on cost of living in their areas has gotten markedly worse over the past decade. Three in four rural voters now say the cost of living in their community is “only fair” or “poor”, a 25-percentage point increase since 2017, when half of rural voters said the same. This includes double-digit increases in the shares of Republican, Democratic, and independent rural voters who rate the cost of living in their community negatively.  

Seven in ten rural voters (72%) also rate job opportunities in their communities negatively, a slight increase from two-thirds (67%) in 2017.

Range plot showing the share of rural voters who rate their community as only fair or poor in 2017 and 2026.

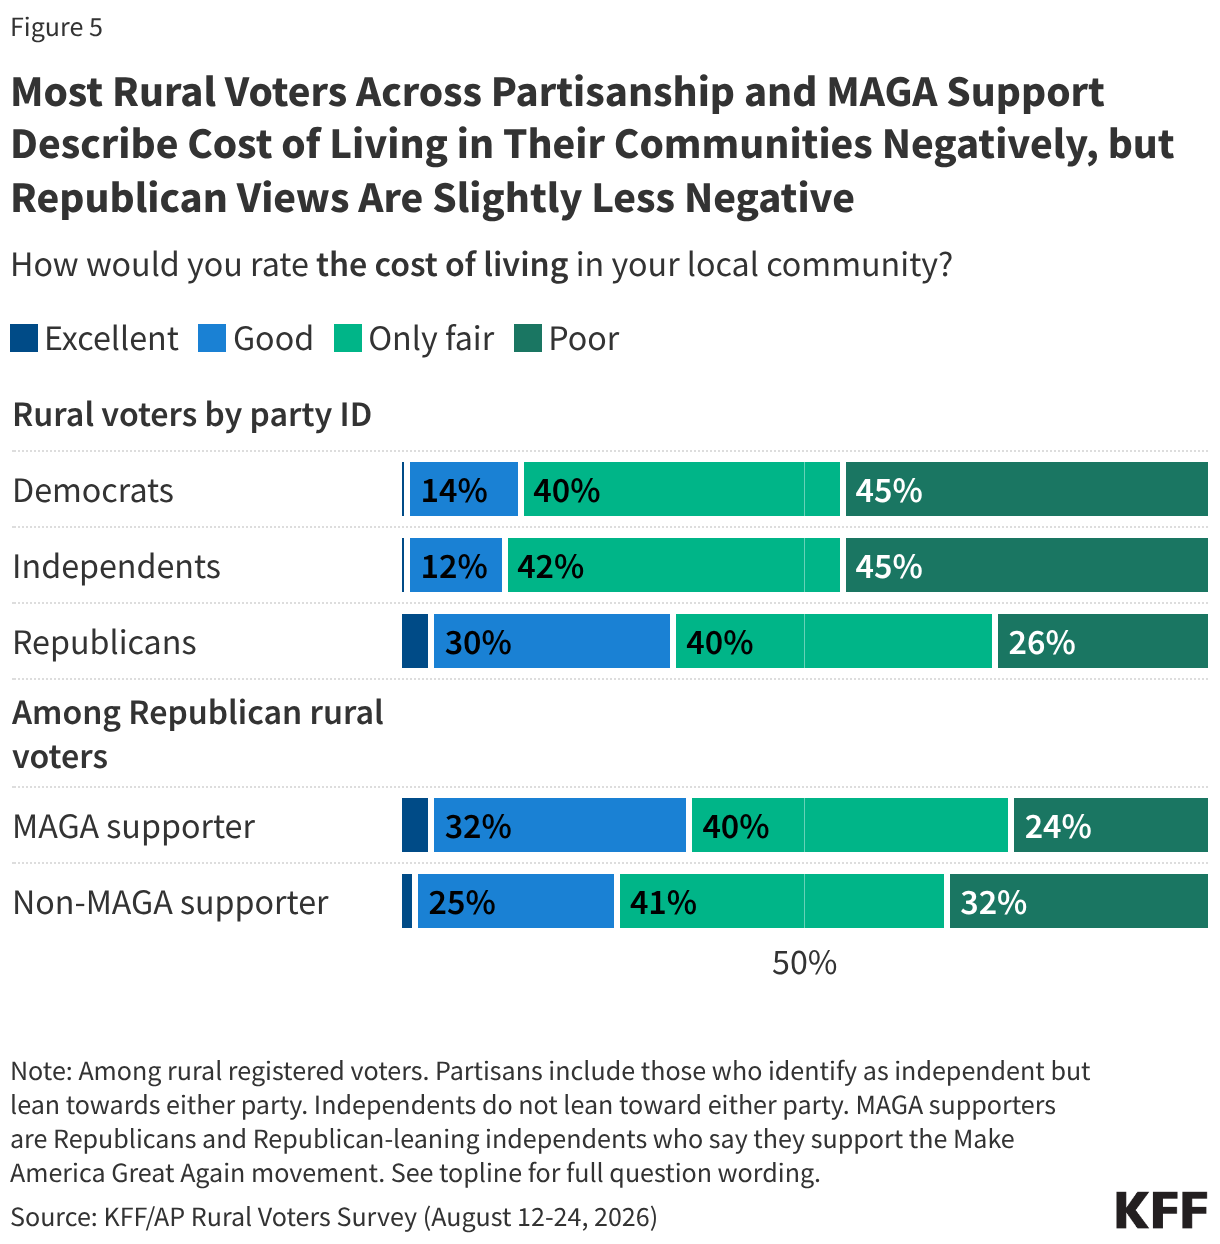
Majorities of rural voters across partisanship describe the cost of living in their community negatively, including more than eight in ten independents (87%) and Democrats (85%) and fewer, but still a majority, of Republicans (66%). Republican rural voters who do not support President Trump’s Make America Great Again (MAGA) movement are somewhat more negative in their views of the cost of living where they live compared to MAGA supporters (73% v. 64%).

Stacked bar chart showing how rural voters rate the cost of living in their community. Results shown among party identification and Republican MAGA and non-MAGA supporters.

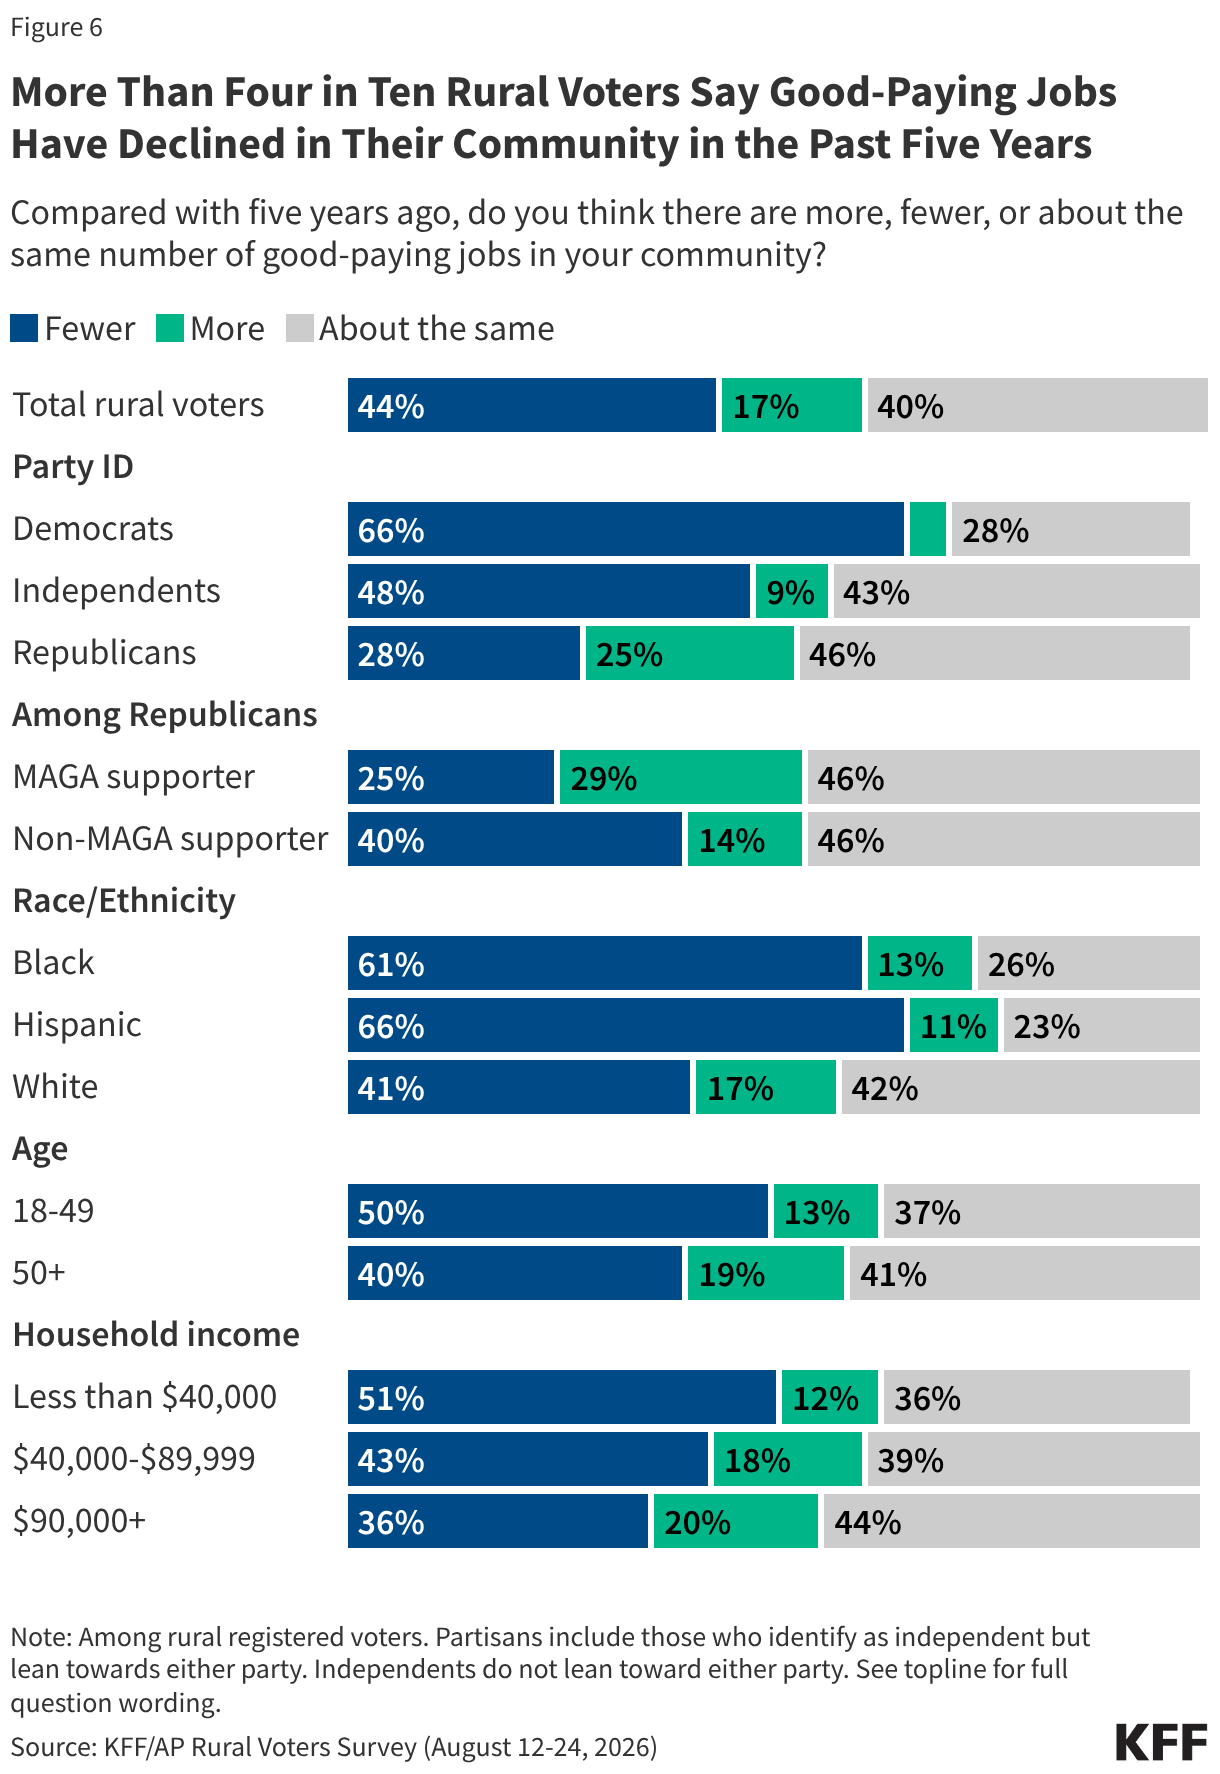
A plurality of rural voters say good-paying jobs have faded in their communities in the past five years. Overall, more than four in ten (44%) say there are fewer good paying jobs in their community compared to five years ago, while just one in six (17%) say there are more of these jobs. Another four in ten say the number of well-paid jobs in their area is about the same as it was five years ago. 

Democratic and independent rural voters are more likely than their Republican counterparts to say good-paying jobs have waned in their communities in the past five years, but similar to dynamics seen on other economic sentiments, non-MAGA supporting Republicans are nearly twice as likely as MAGA supporting Republicans to say good-paying jobs have declined where they live. Views that good-paying jobs have declined in their community are also held by larger shares of rural voters who are Hispanic (66%), Black (61%), have annual household incomes below $40,000 (51%), or are under age 50 (50%) compared to their counterparts.

Stacked bar chart showing the share of rural voters who think there are fewer, more, or about the same number of good paying jobs in their community compared to five years ago.

More than four in ten (44%) rural voters say their local economy has gotten worse during the second Trump presidency, including eight in ten (82%) Democratic rural voters, half (51%) of independents, and one in five (19%) Republican rural voters, though this rises to a third (35%) among non-MAGA supporting Republicans.

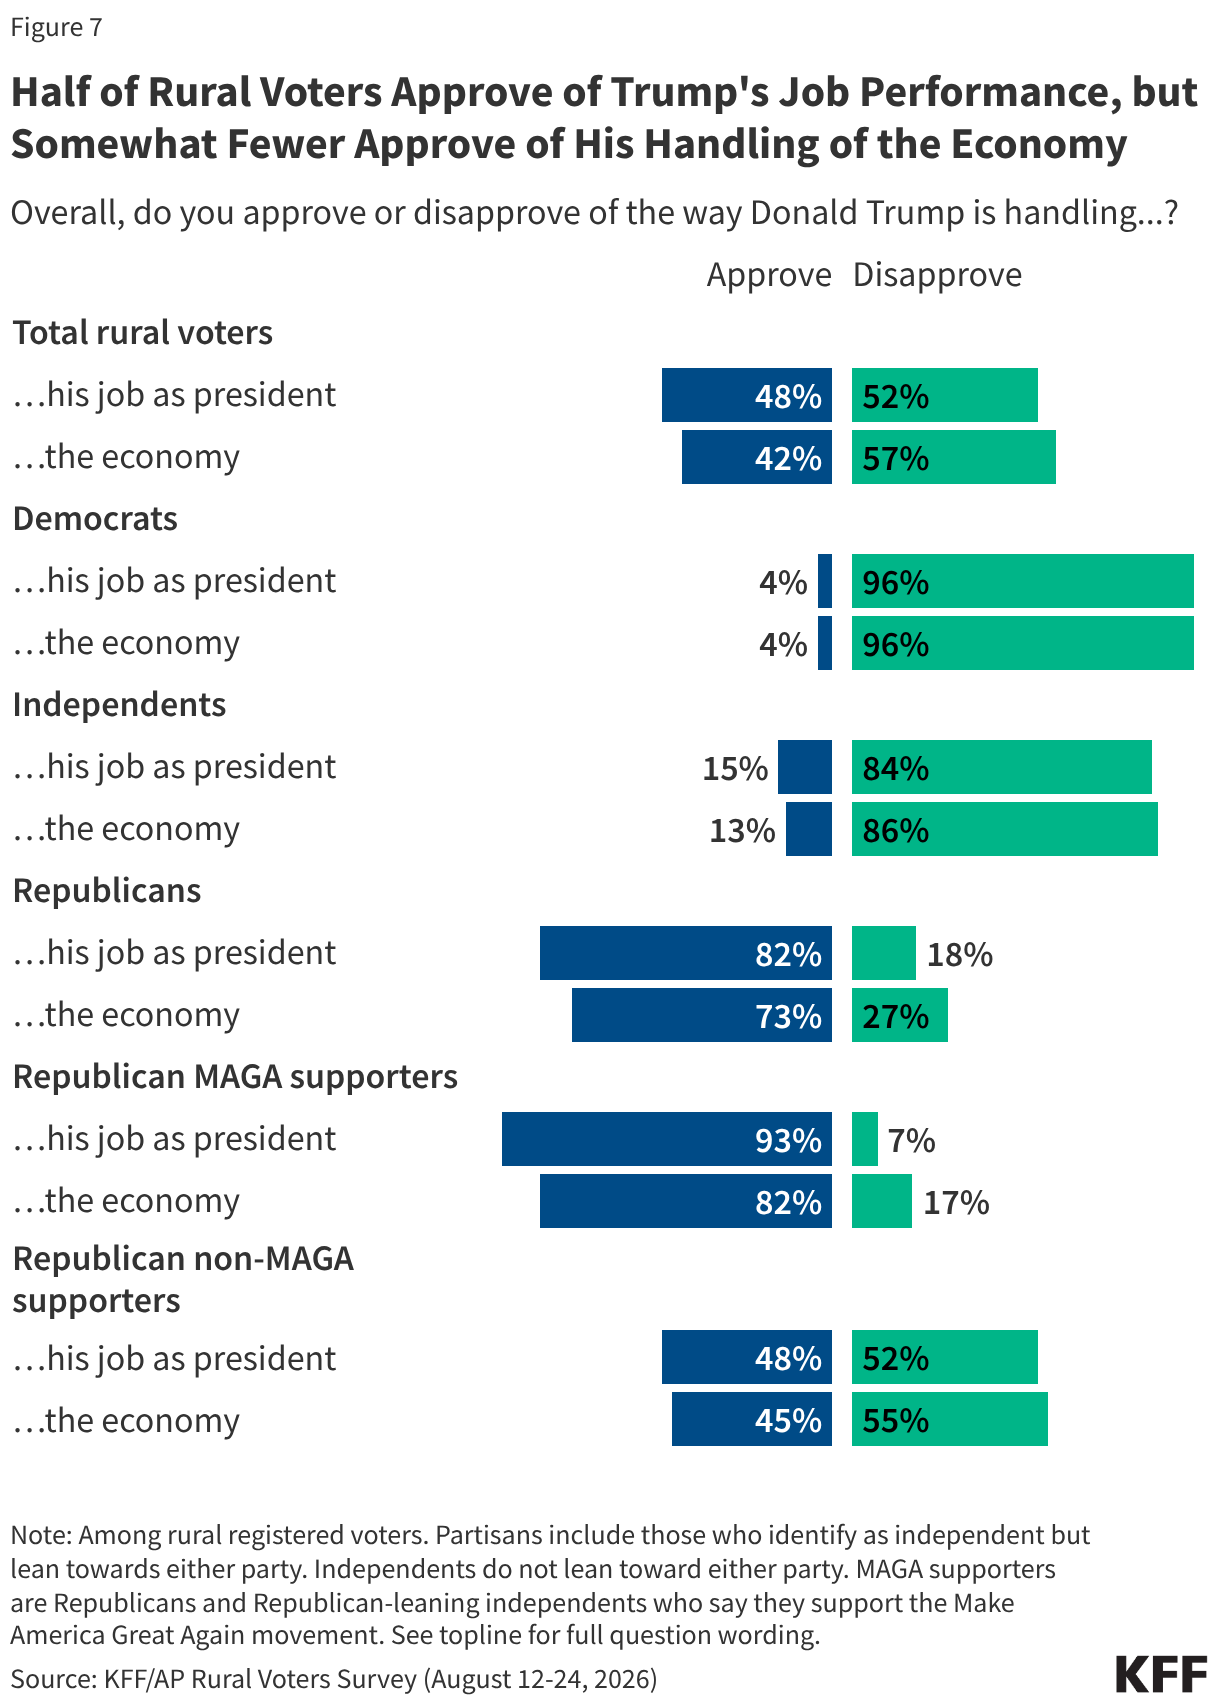
All of these negative economic sentiments may be contributing to rural voters’ views of President Trump overall and on the economy. About six in ten rural voters (57%) disapprove of President Trump’s handling of the economy. While about half (48%) of rural voters approve of his overall job performance, this has dropped slightly from a similar question asked in 2017, when 56% of rural registered voters said they approved. Notably, a larger share of Republican rural voters disapprove of President Trump’s handling of the economy (27%) than of his overall job performance (18%).

For Republican rural voters, however, approval of President Trump varies widely between MAGA supporters and non-MAGA supporters, suggesting that the President’s approval among rural Republicans outside his core base is much weaker. Half or more non-MAGA Republican rural voters (who make up a quarter of Republican rural voters overall) say they disapprove of the president’s job performance (52%) and his handling of the economy (55%) compared to one in six or fewer MAGA-supporting Republicans.

Split bar chart showing the share of rural voters who say they approve or disapprove of the way Donald Trump is handling his job as president and the economy. Results shown by party identification and MAGA support.

Republican Rural Voters Sour on the Economy May Not Turn Out in 2026

While the overwhelming majority (98%) of rural Republican voters say they would be more likely to vote for a Republican candidate than a Democrat in the upcoming election, dissatisfaction with President Trump’s handling of the economy may be impacting some Republican rural voters’ motivation to turn out for the 2026 midterms.

Republican rural voters overall are somewhat less likely than Democrats to say they are “absolutely certain” to vote in the upcoming election (74% vs. 81%). Further, Republicans who say they disapprove of Trump’s handling of the economy (27% of Republican rural voters overall) are 20 percentage points less likely than those who approve of his handling of the economy to say they are “absolutely certain” to vote (59% vs. 79%).

Bar chart showing the share of rural voters who say they are absolutely certain they will vote in the 2026 midterm elections. Results shown by party identification and republicans who approve and disapprove of Trump's handling of the economy.

Health Costs and Price of Gas Top Household Affordability Worries

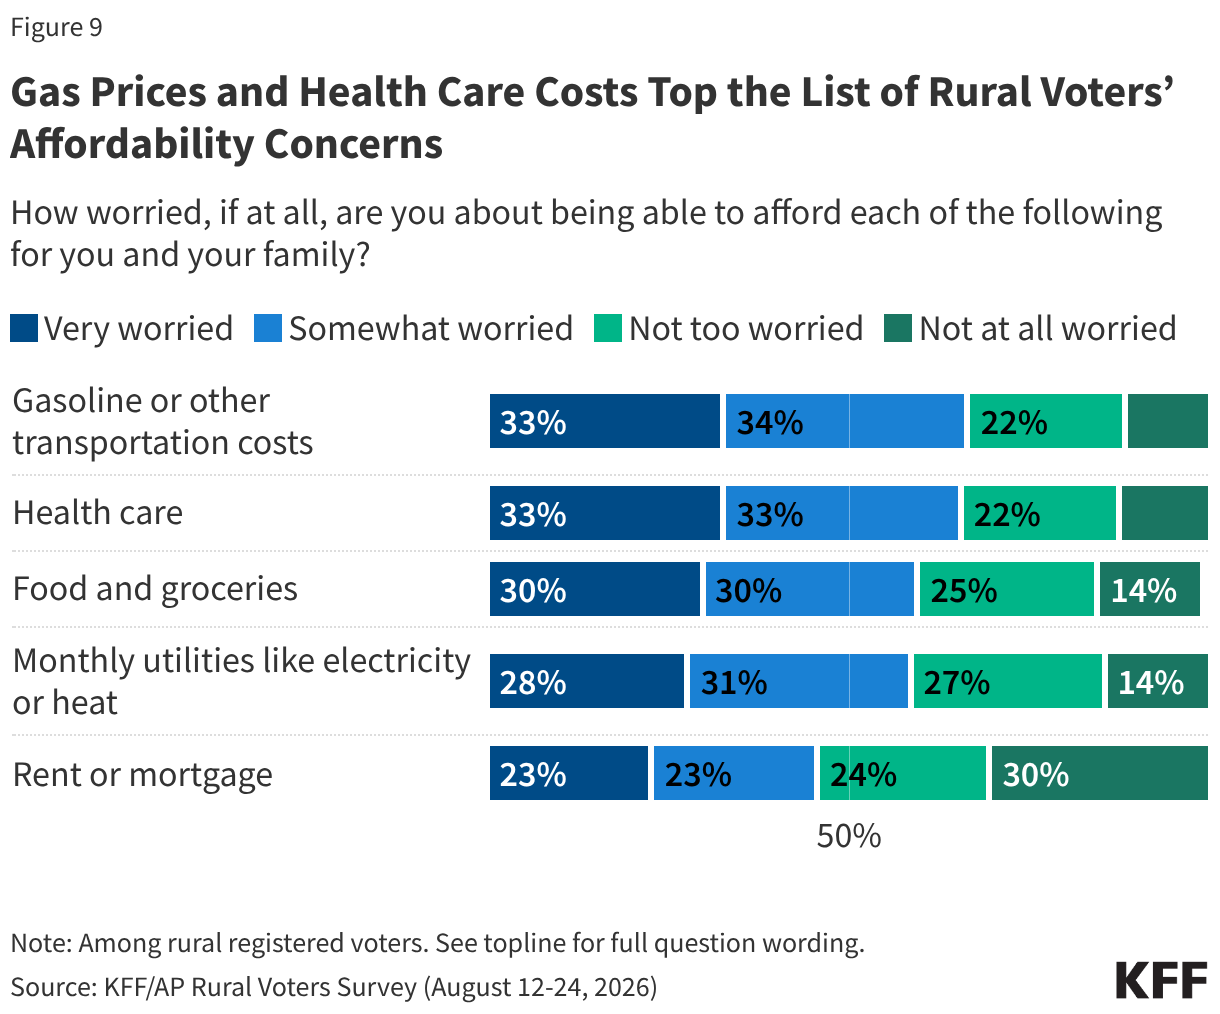
While rural voters express concern about affording a wide range of household necessities, health care costs and the price of gasoline top the list. Two-thirds of rural voters say they are either “very” or “somewhat worried” about being able to afford gasoline or transportation costs (67%) or health care (66%) for themselves or their families. Somewhat smaller majorities express worry about affording food and groceries (60%) or monthly utilities (59%), while nearly half (46%) are worried about affording their rent or mortgage.

While health care costs and gas remain the top affordability concern across partisanship, as with other economic sentiments, Democratic voters in rural areas are more likely than their Republican counterparts to express affordability worries across the board. Likely reflecting their lower incomes, younger rural voters are also more worried than older voters about being able to afford a variety of expenses. But for the youngest cohort of rural voters under age 30, health care costs rise to the top of their economic concerns, with about three quarters (77%) saying they are worried about affording health care for themselves or their families.

Stacked bar chart showing how worried rural voters are about being able to afford household essentials.

Who Voters Trust to Handle Key Issues

The Republican Party has an advantage when it comes to which party rural voters trust more to address the cost of living – rural voters’ top election priority – but voters are more divided on which party they trust to address health care costs, a key factor in their affordability concerns. At the same time, at least a quarter of rural voters say they prefer neither party across these issues.

Overall, four in ten rural voters say they trust the Republican Party to do a better job handling the cost of living, compared to a quarter who trust the Democratic Party and another quarter (27%) who trust neither party.

The Republican Party has a much narrower advantage on health care costs.  One-third of rural voters say they trust the Republican Party more to handle health care costs compared to about three in ten (28%) who trust the Democratic Party more. And similar shares of rural voters say they prefer the Democrats and the Republicans on handling Medicaid, Medicare, and the Affordable Care Act, while at least a quarter say they trust neither party to handle each of these health care programs.
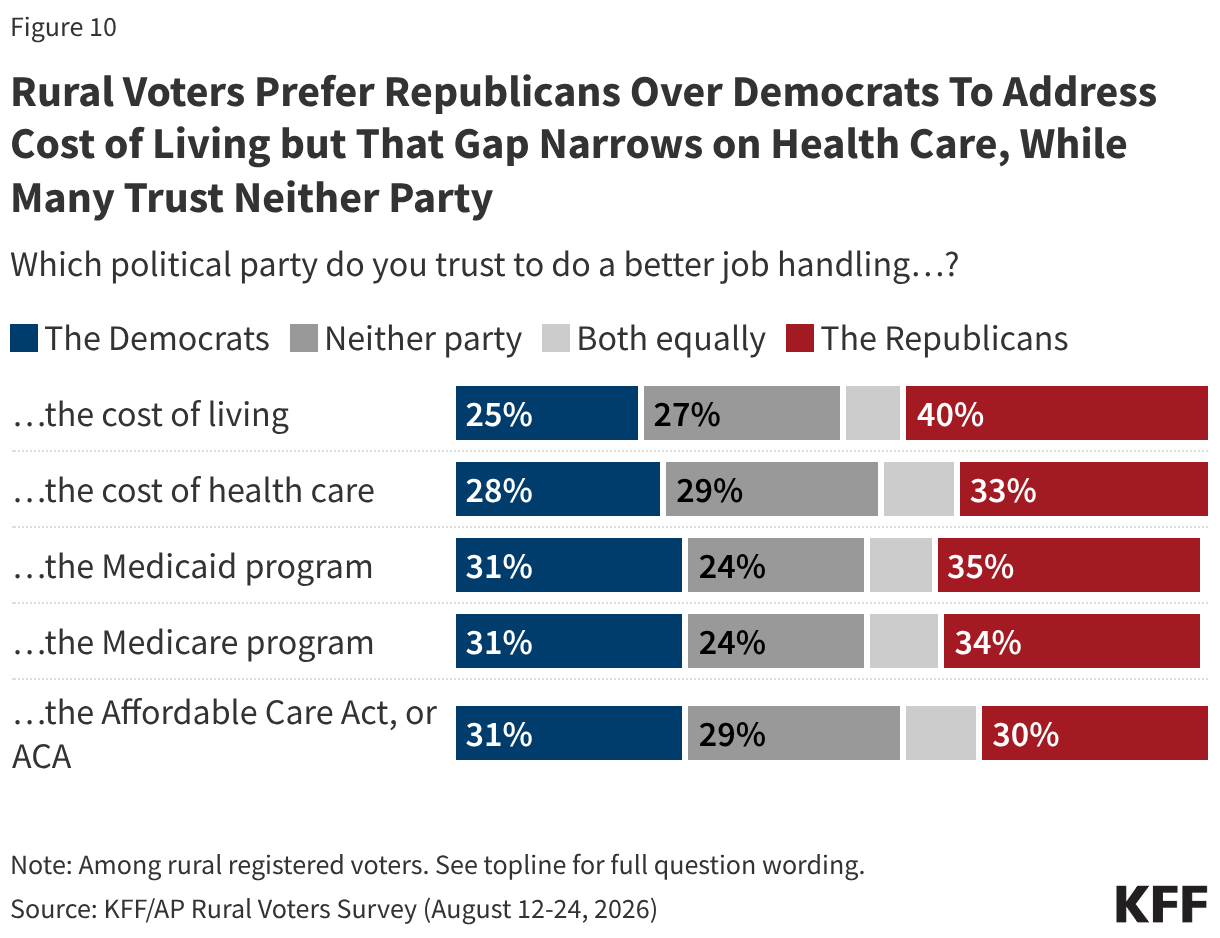
Stacked bar chart showing which party rural voters trust to do a better job handling the cost of living and health care issues.

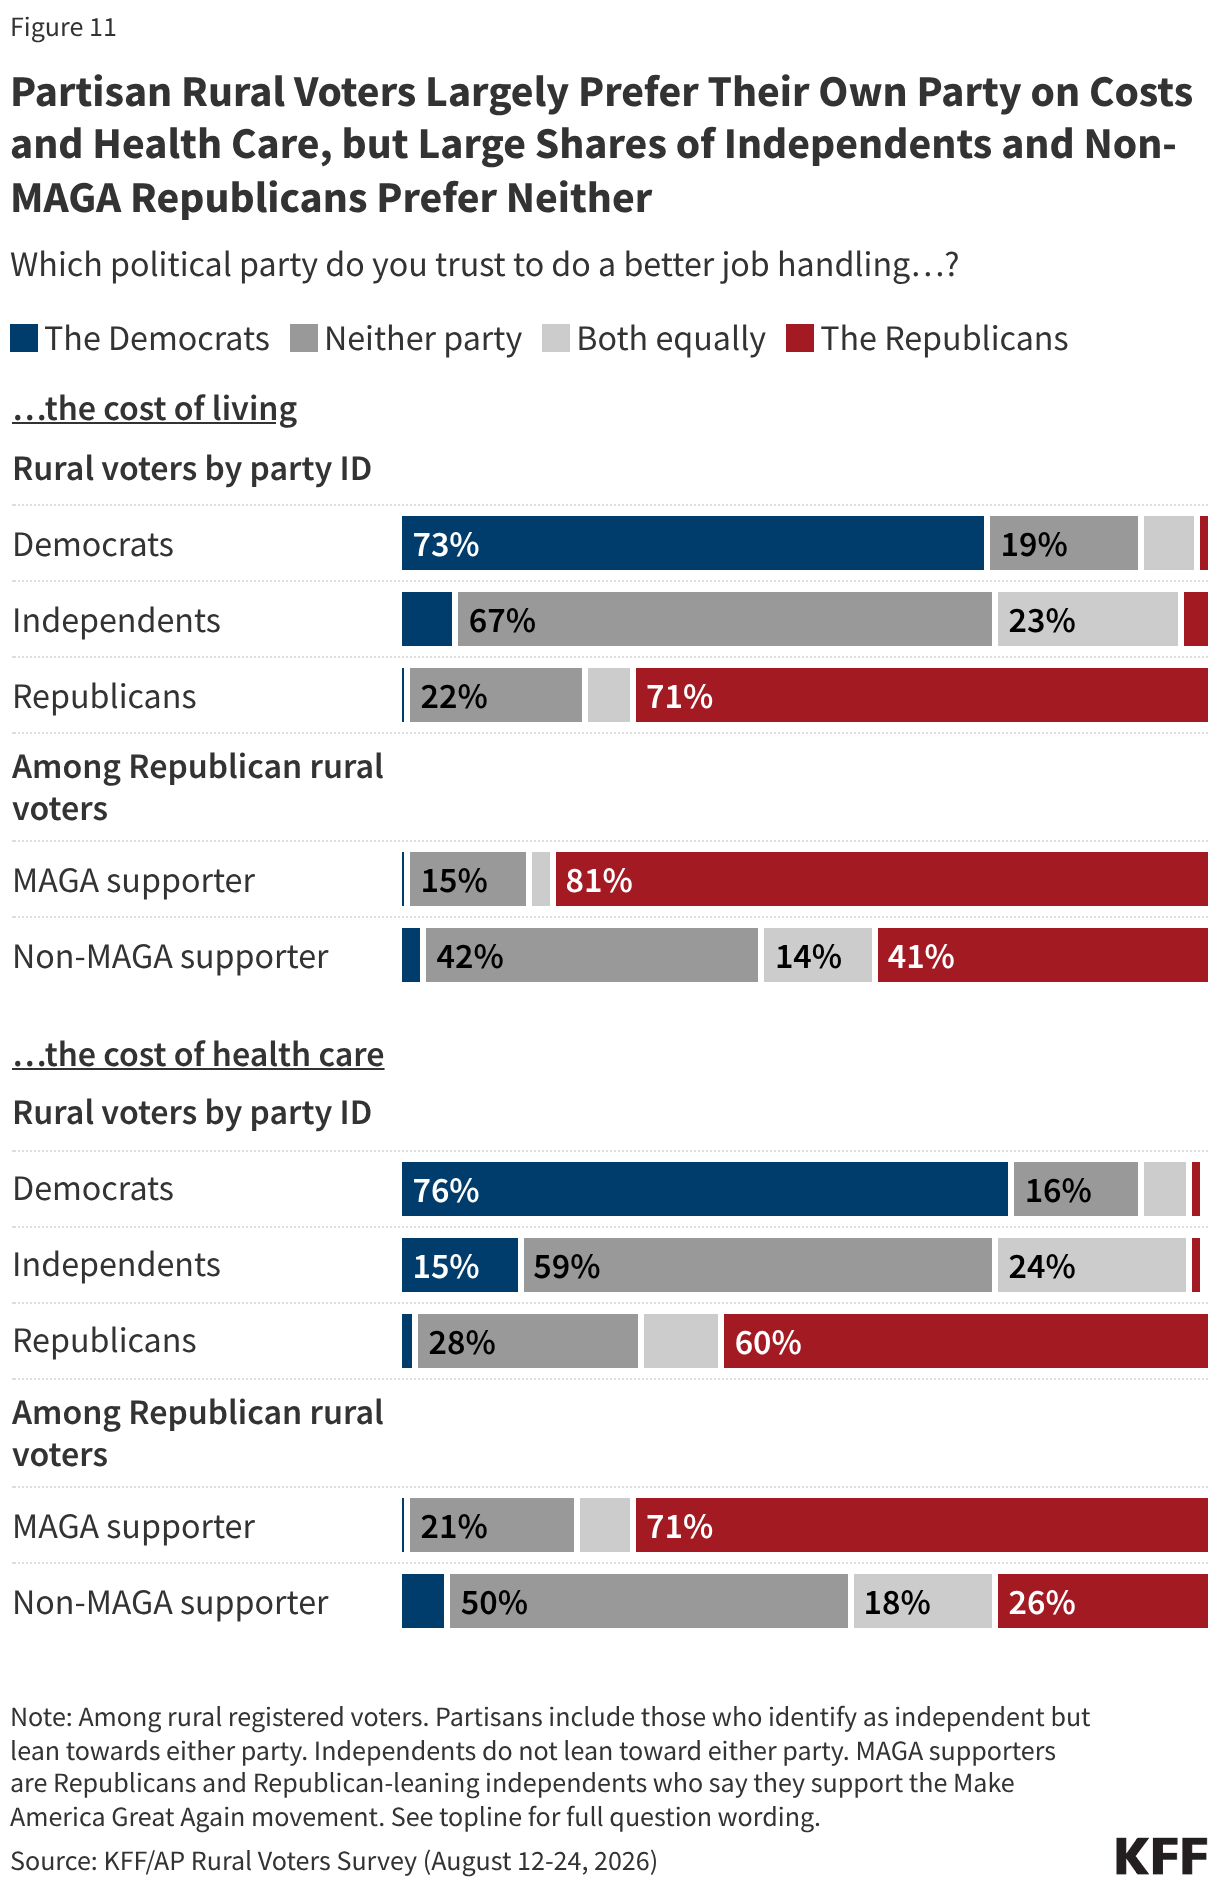
Partisans largely pick their own party on handling cost of living and health issues. For health-related issues, the Democrats tend to have a stronger advantage with their own rural voters than Republicans do with theirs, and this drops to fewer than half among non-MAGA supporting Republicans. For example, three-quarters (76%) of Democratic rural voters say they trust the Democratic Party to do a better job handling health care costs, while a smaller share (60%) of Republican rural voters say the same about the Republican Party, dropping to a quarter (26%) among non-MAGA supporting Republicans. Republican rural voters who do not support the MAGA movement largely still do not prefer Democrats, but rather say they trust neither party to handle costs.

While small shares of independent rural voters prefer the Democratic Party over the Republican Party to address the cost of health care, majorities of these independents say they trust neither party to address cost of living or health care cost (67% and 59%, respectively).

Stacked bar chart showing which party rural voters trust to do a better job handling the cost of living and the cost of health care. Results shown by partisan identification and MAGA support.

Views of Trump Administration’s Recent Changes to Health Care Policies

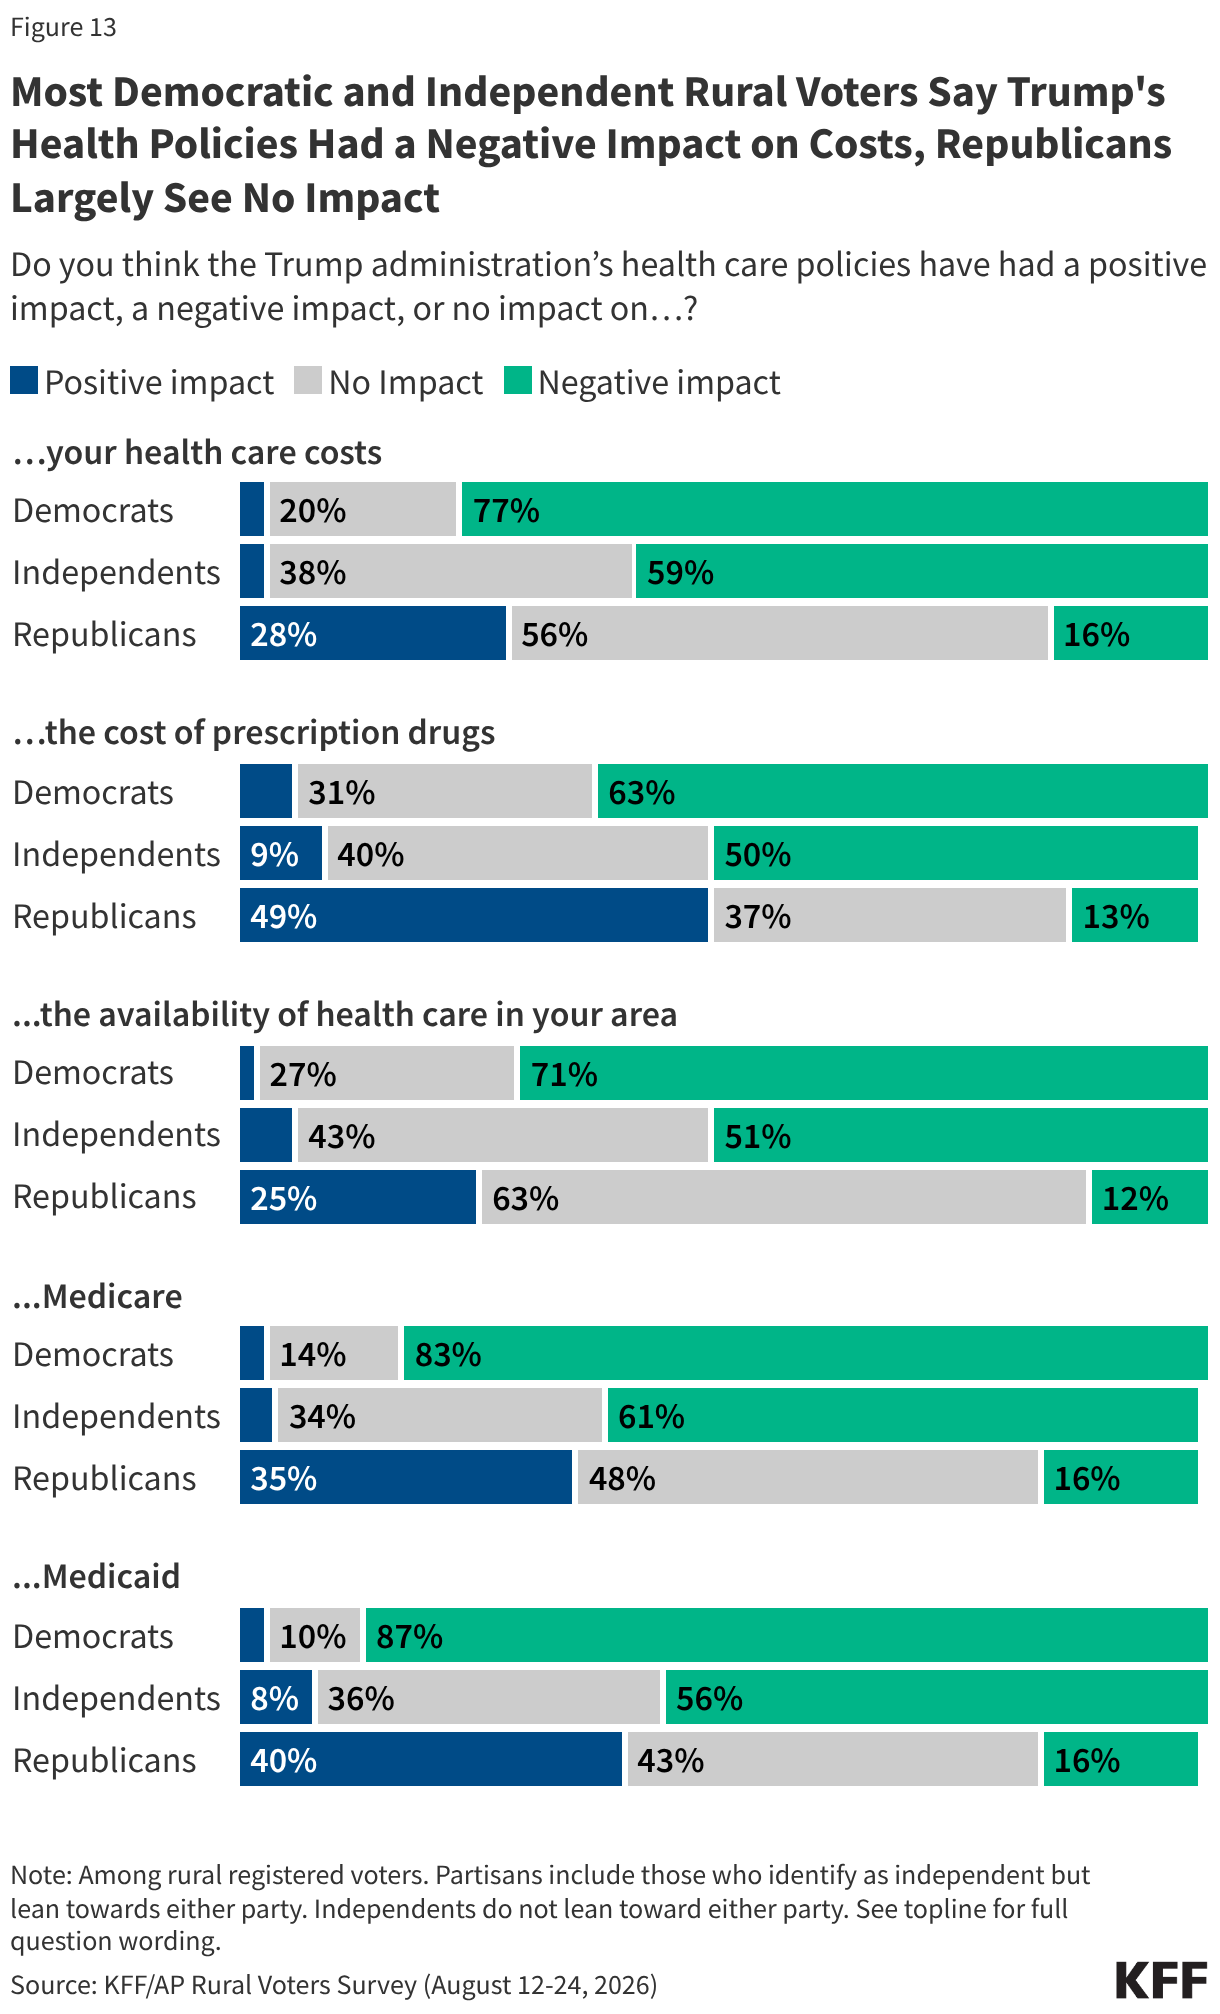
With slightly more than half (54%) of rural voters saying they disapprove of Trump’s handling of health care, views on the impact of the administration’s specific health care policies also skew negative. Roughly twice as many rural voters say the Trump administration’s health care policies have had a negative impact rather than a positive impact when it comes to their own health care costs (41% v. 17%), Medicare (44% v. 21%), Medicaid (44% v. 24%), and the availability of health care in their area (37% vs. 15%). Between three in ten and half of rural voters say the administration’s health care policies have had “no impact” in each of these areas. Views are slightly more divided on the impact of the administration’s policies on prescription drug costs, with three in ten (30%) saying the impact has been positive and about one-third each saying it has been negative (35%) or had no impact (35%).
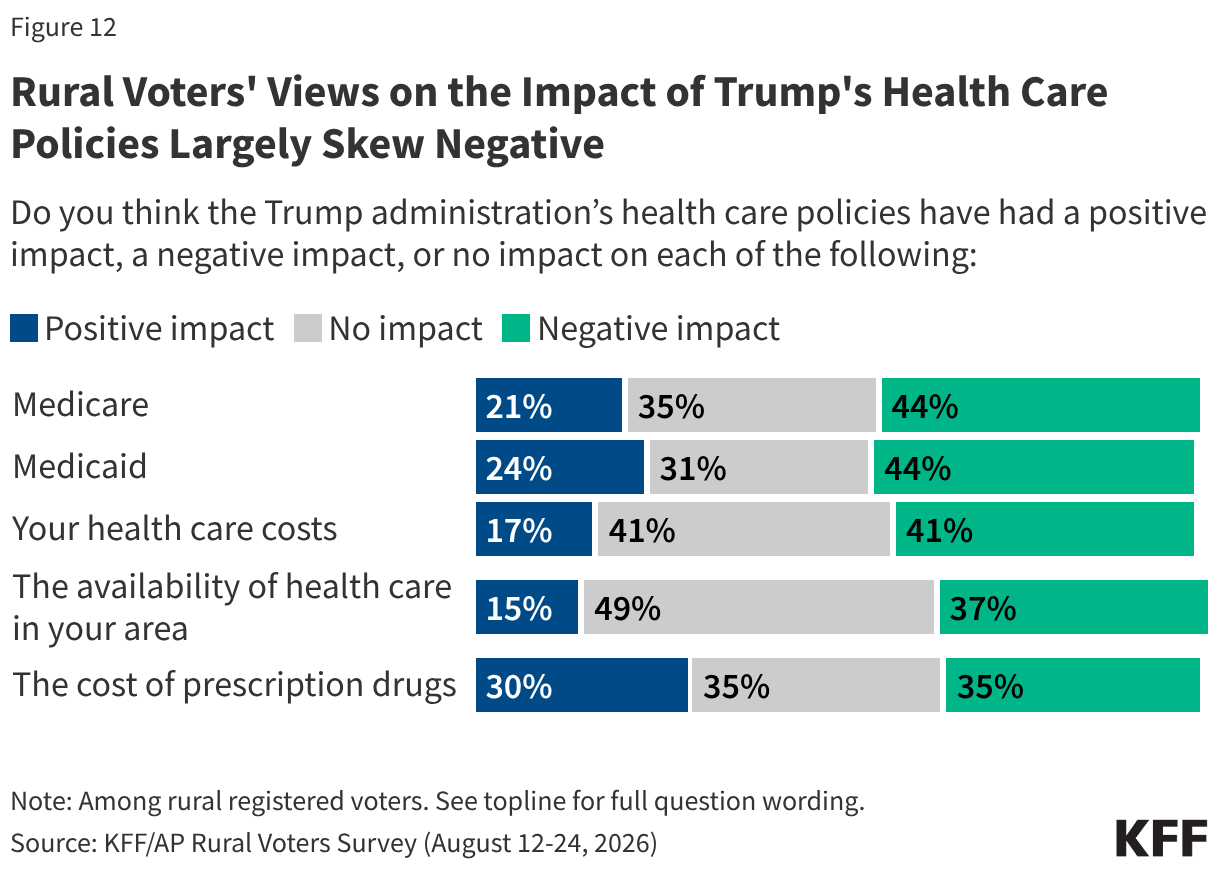
Stacked bar chart showing how much impact rural voters believe the Trump administration's health care policies have had.

Partisans’ views are unsurprisingly divided on the impact of Trump’s health care policies, with most Democratic voters and at least half of independent voters saying they’ve had a negative impact. While Republican rural voters are less negative in their views, they are not overwhelmingly positive, either: over half say the administration’s policies have had “no impact” on their own health care costs, or the availability of health care in their area. Republican rural voters are somewhat more positive when it comes to the impact of the administration’s policies on Medicaid, with four in ten saying the impact has been positive, 16% viewing it as negative, and another four in ten (43%) saying there has been no difference.

Most (57%) rural voters who purchase their own health coverage (10% of rural voters overall) say the administration’s health care policies have negatively impacted their health care costs, higher than the share of rural voters with employer sponsored insurance or Medicare. This likely reflects the impact of rising costs for those who purchased coverage through the ACA Marketplaces following the expiration of enhanced premium tax credits last year.

Stacked bar chart showing whether rural voters believe the Trump administration's health care polices have had an impact. Results shown by party identification.

Medicaid’s Role for Rural Voters

Roughly half (49%) of rural voters say they or a family member have gotten support from the Medicaid program at some point in their lives, including four in ten (38%) who say they or a family member currently receives some form of coverage through the program. More than half of rural voters who are Hispanic (72%), Black (67%), under age 30 (65%), or women (56%) say they or someone in their family has ever gotten coverage from Medicaid, with at least four in ten across partisanship saying the same.

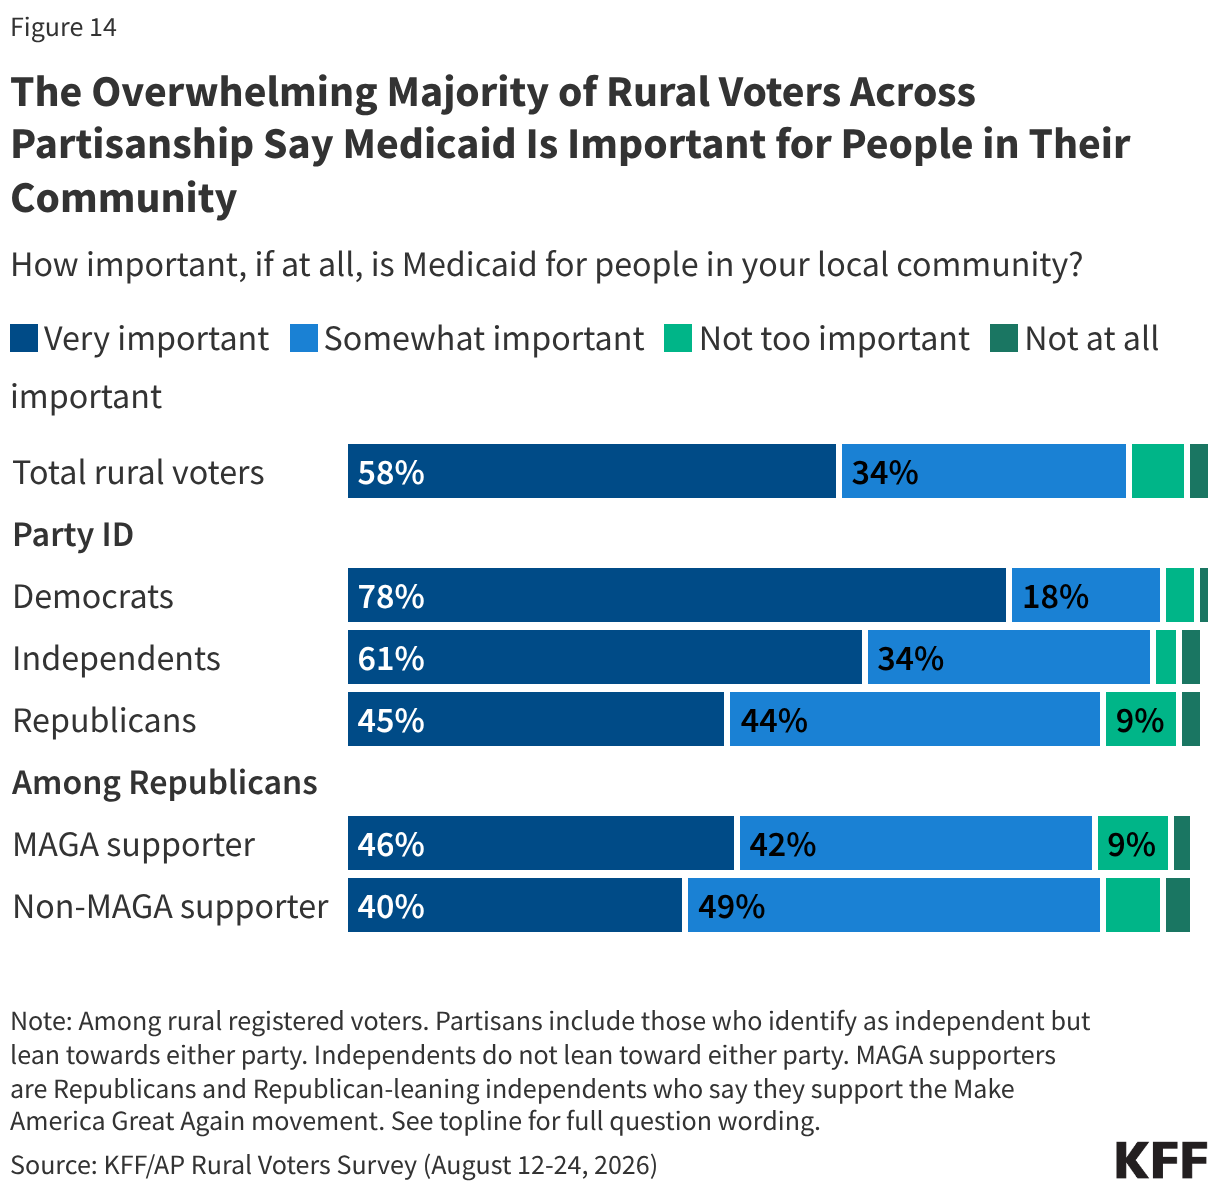
Similar to sentiments held by the general population, nine in ten (92%) rural voters, including large majorities across partisanship and among Republican MAGA supporters say Medicaid is important for people in their local community.

Stacked bar chart showing how important rural voters believe Medicaid is for their local community. Results shown by party identification and MAGA support.

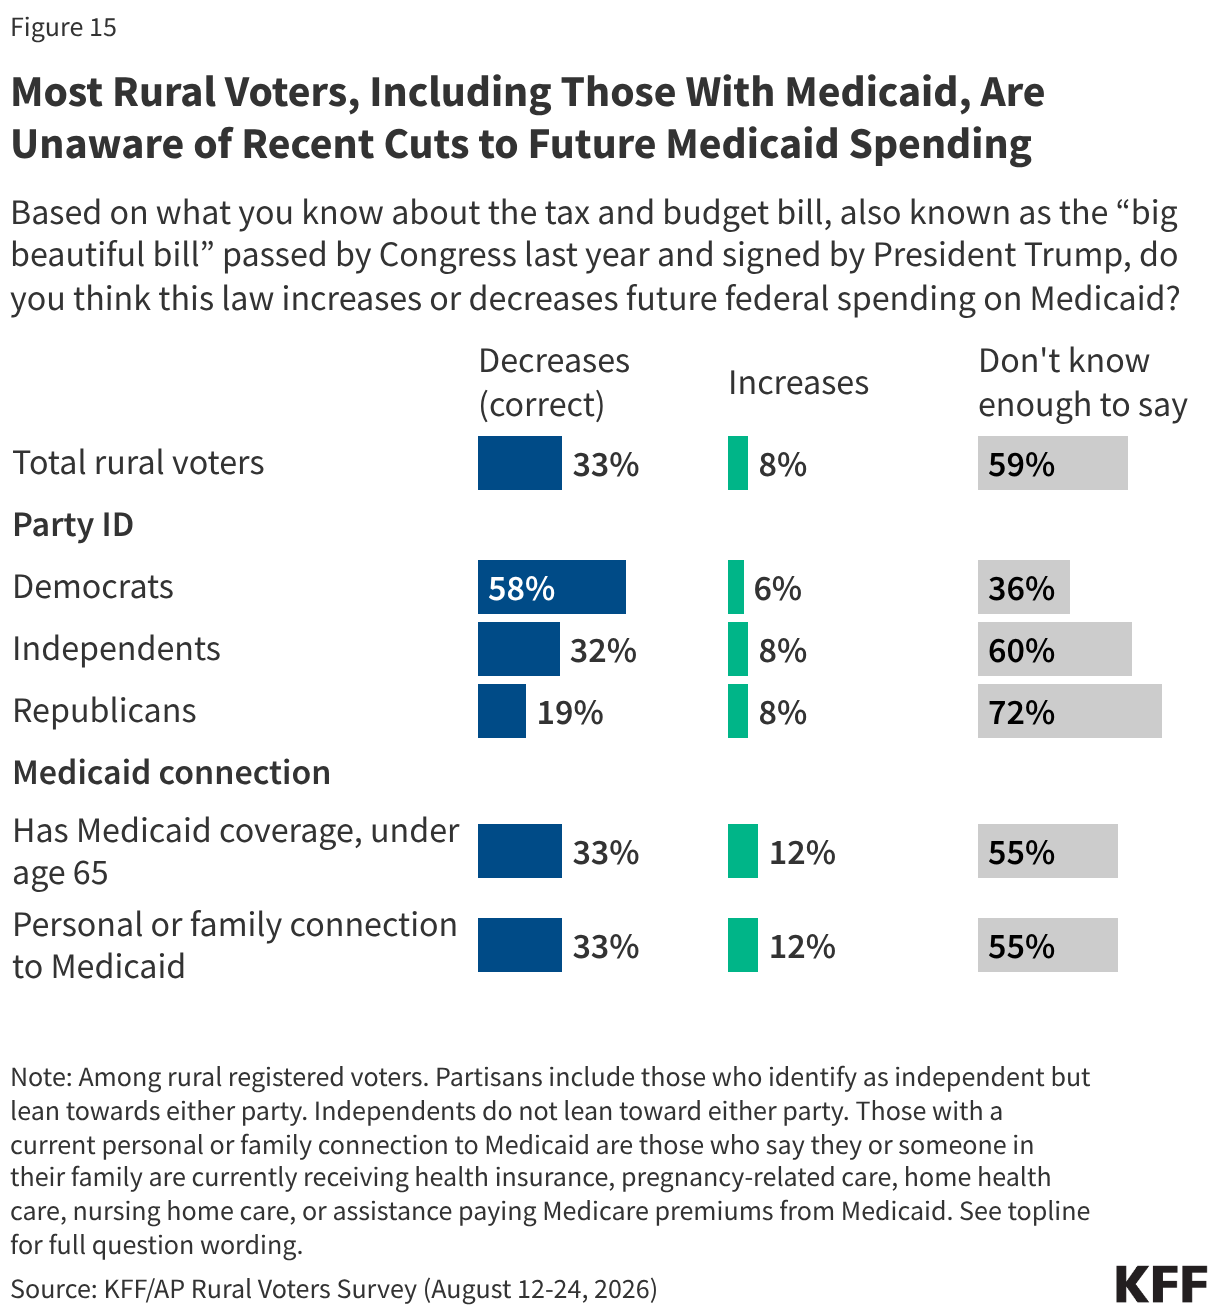
In late 2025, Congress passed and President Trump signed into law a legislative package known as the “One Big Beautiful Bill,” that included significant changes to the Medicaid program including reducing future federal spending on the program by more than $900 billion.

Awareness of reduced Medicaid funding among rural voters is low, with just one-third correctly saying the bill decreases future spending on Medicaid while six in ten (59%) say they don’t know enough to say, including more than seven in ten Republican voters.

Split bar chart showing the share of rural voters who believe the big beautiful bill decreased or increased federal spending on Medicaid.

During the drafting of the 2025 budget bill, lawmakers added $50 billion in funding for a Rural Health Transformation Program, or “Rural Health Fund,” in response to concerns over the impact that reductions in health spending could have in rural areas. Most rural voters, however, remain unaware of the fund, with more than eight in ten saying they have heard either “a little” (23%) or “nothing at all” (61%) about the program. More than half of voters across partisanship say they have heard “nothing at all” about this fund.
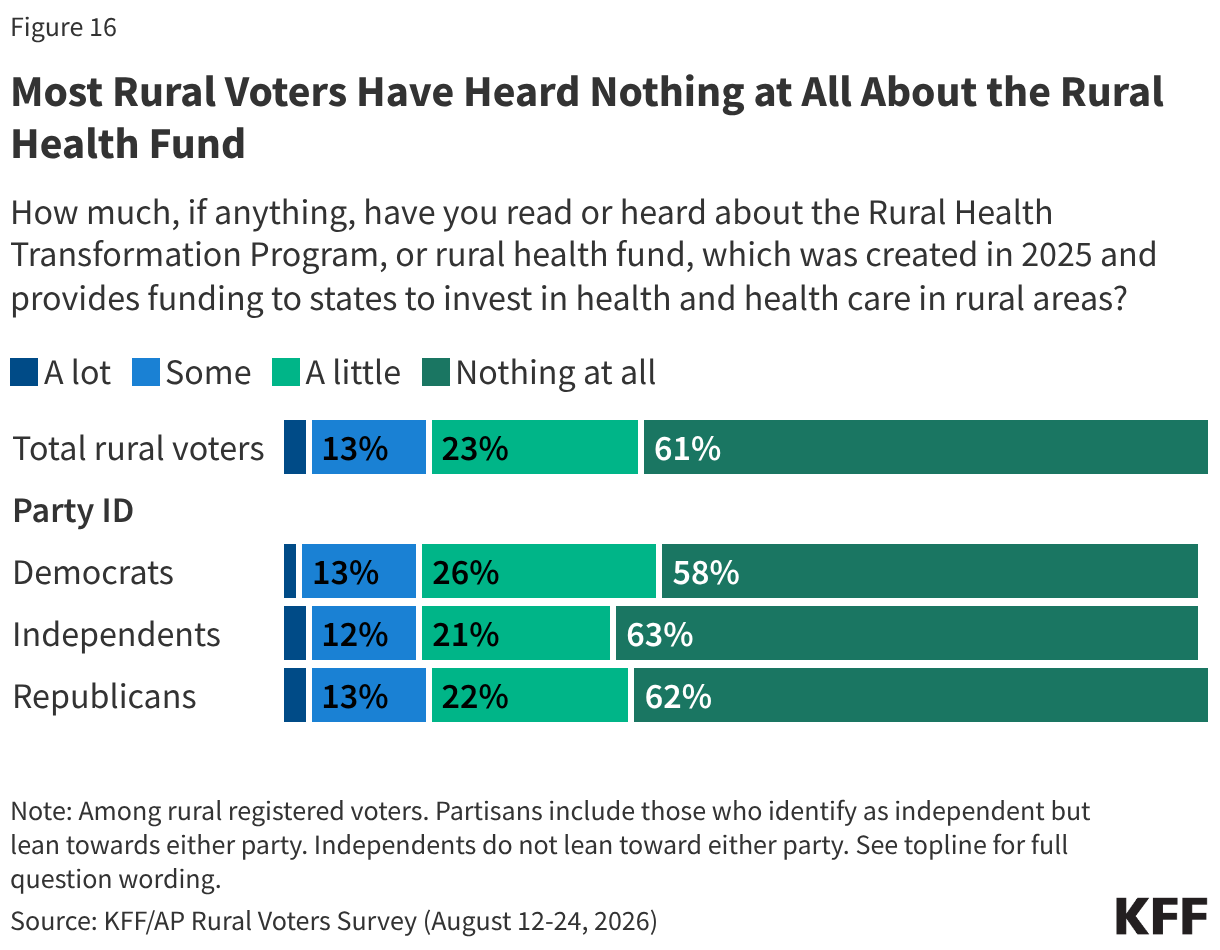
Stacked bar chart showing how much rural voters have heard about the Rural Health Transformation Program. Results shown by total rural voters and party identification.

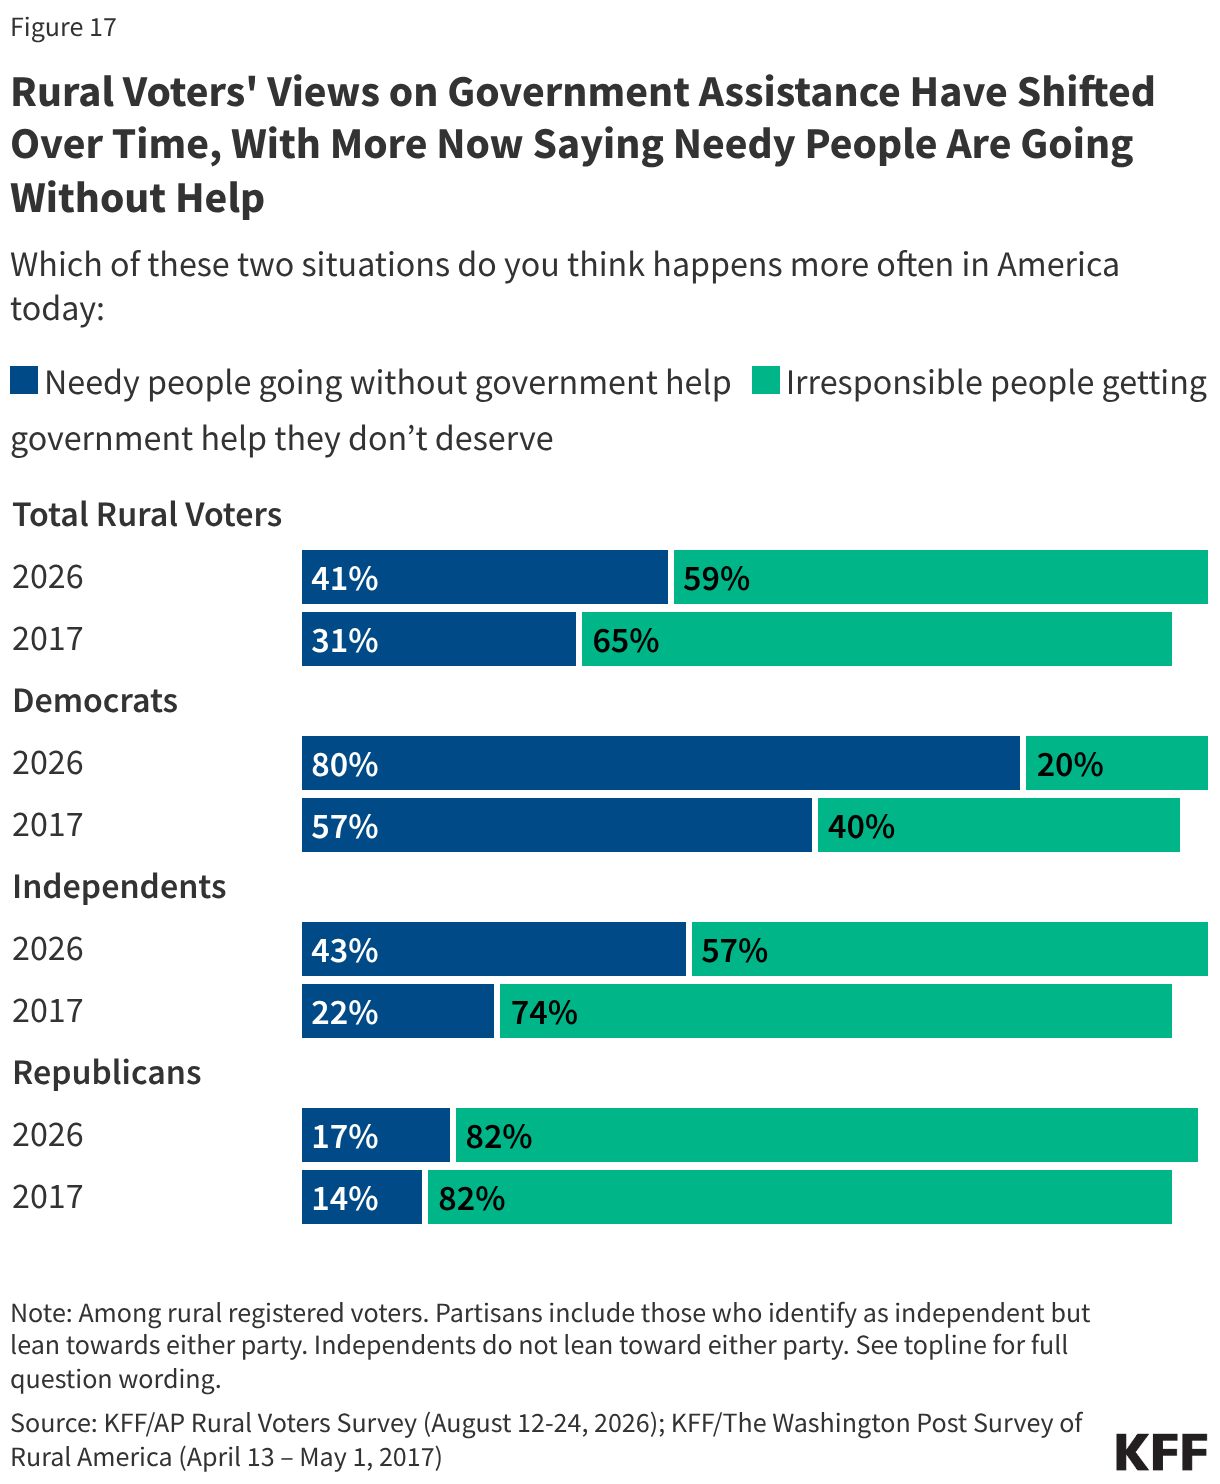
A majority of rural voters say it’s more often that government assistance goes to undeserving people, though their views on this have softened somewhat over the years. Six in ten (59%) rural voters say it’s more common in America that “irresponsible people get government help they don’t deserve” compared to four in ten (41%) who say it’s more common that “needy people go without government help.” These views have shifted moderately among rural voters over the past nine years, with a 10-percentage point rise in the share who say it’s more common that needy people are going without help. These sentiments have shifted most dramatically among Democrats and independents, while Republicans’ views have largely remained unchanged.

For Republican rural voters, having a current connection to the Medicaid program appears to soften their views on government assistance more broadly: Republicans who say they or a family member are currently receiving some type of Medicaid coverage are three times as likely as those with no such current connection to say it’s more common in America that people are going without government assistance they need (33% v. 10%).

Stacked bar chart showing the share of rural voters in 2017 and 2026 who believe needy people going without government help or irresponsible people getting government help they don’t deserve, happens more often in America today.

A Growing Share of Rural Voters Say Their Communities Lack Key Health Care Services

Rural areas in the U.S. can face unique health care challenges, including provider shortages, lack of internet access, and hospital closures. The KFF/AP Rural Voters Survey shows that many rural voters rate health care in their communities poorly, a sentiment shared by Democrats, independents, and Republicans. As with other economic sentiments, views on the availability of some health care services have worsened over the years.

Many rural voters say their communities lack sufficient health care services and providers to serve local residents, including mental health care providers (62%) and doctors or other health care providers (46%). While most rural voters say their communities have enough pharmacies (81%) or hospitals (65%) to serve local residents, a notable share (35%) say their communities do not have enough hospitals, rising to half among Black (52%) and Hispanic (52%) rural voters.

Rural voters’ perceptions of the availability of doctors and hospitals have worsened since 2017 overall and across partisans, however the rise in the share saying their community lacks enough providers and hospitals has been steeper among Democrats than among Republicans. Between 2005 and 2026, nearly 200 rural hospitals have closed or converted, with closures recently outpacing openings in rural areas.
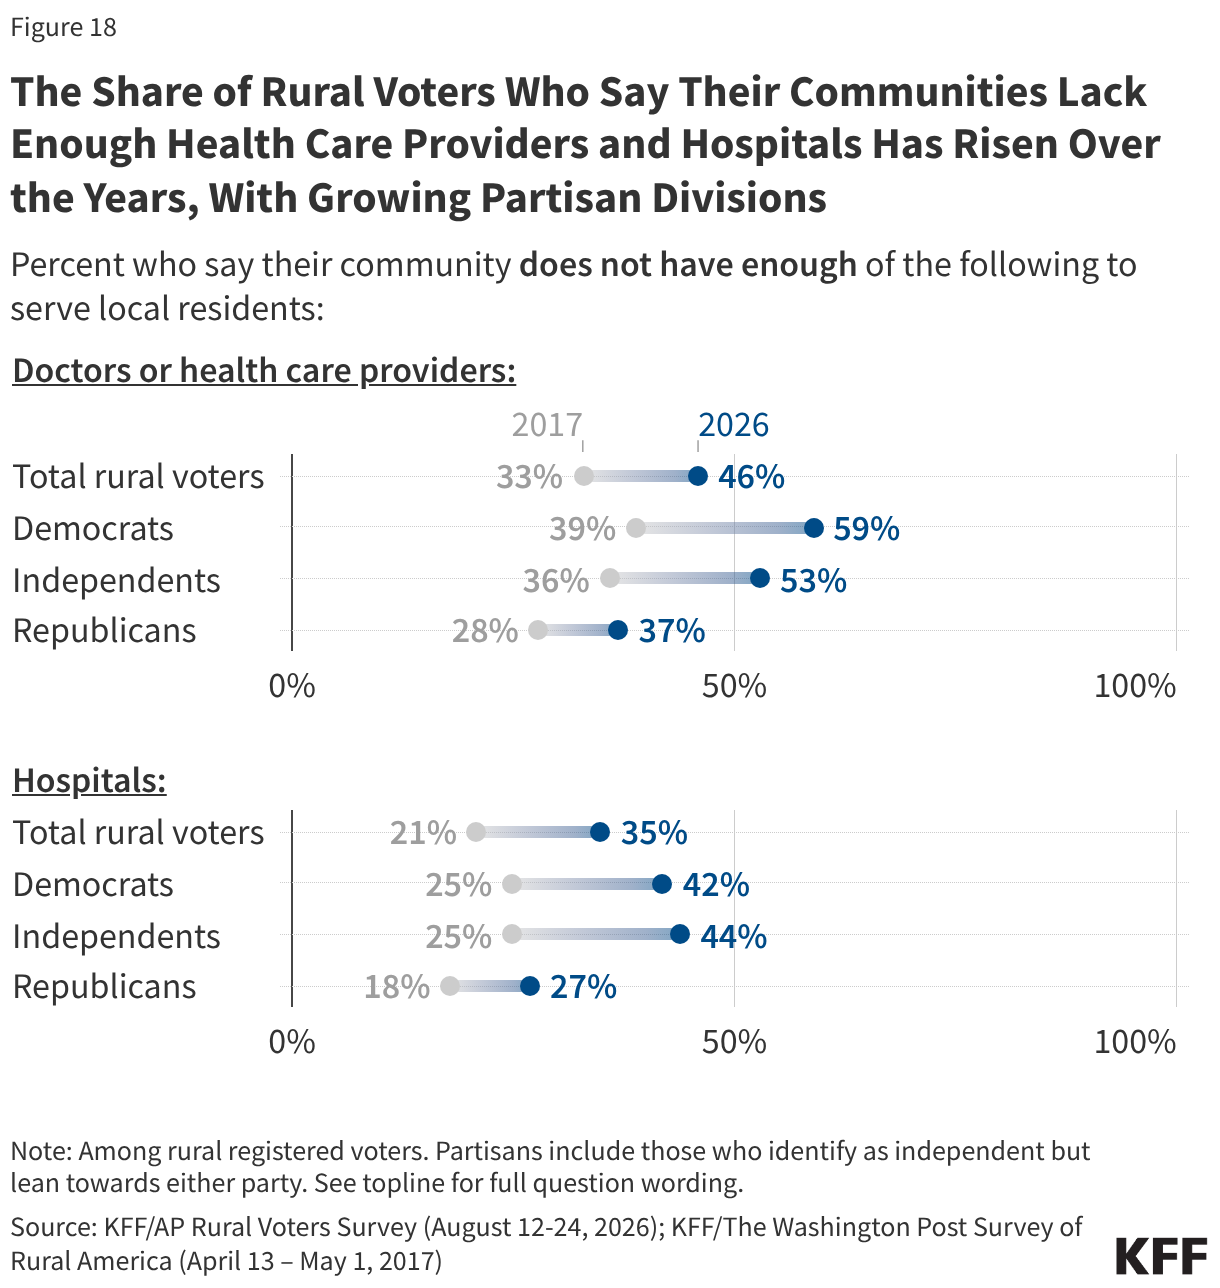
Range plot showing the share of rural voters in 2017 and 2026 who say their community does not have enough doctors or hospitals.

In Their Own Words: Rural Voters Who Say Health Care-Related Issues Are the Biggest Problem Facing Their Community

“We need more help affording healthcare for our family.  Our health insurance tripled this past year and we can barely afford to pay for it plus afford food!   We were hoping Trump, with his business sense would figure out a way that every person in the country would have health insurance, the price of food would finally come down, and the price of gas would be at its lowest ever.  Instead, we are at war…” – 54-year-old rural voter from Wisconsin, Republican

“No decent permanent facilities for the elderly. There's one really nice place that only the rich can afford. The hospital emergency room is horrific, at times there are very sick individuals in the waiting room or on stretchers in the hallway.” – 67-year-old rural voter from Tennessee, Republican

“The lack of a living wage is a major issue, but our greatest crisis is the lack of quality healthcare. Those with the ability to travel, go to [nearby cities] for medical care. The local hospital is stocked with part-time traveling nurses, and doctors. There is no stability in healthcare, and I worry that the proposed Medicare, and Medicaid cuts will endanger the future of the hospital.” – 70-year-old rural voter from Texas, Democrat

“There's a somewhat vague sense of dreadful anticipation that our small rural community is going to lose its hospital due to Trump and his administration's cuts, which apparently kick in on January 1, 2027.  The hospital employs a great many people and it is the only reasonable option for emergency care and other kinds of medical services for about a 25 to 30 miles radius.” – 64-year-old rural voter from New York state, Democrat

Note: Responses are lightly edited for length and spelling, but reflect respondents' own language and do not represent the views of KFF.

  1. Throughout this report, Democratic and Republican rural voters include those who identify as independent but lean towards either party, respectively. Independents are independent rural voters who do not lean toward either party. ↩︎

The KFF/AP Rural Voters Survey examines the views and political priorities of voters living in rural areas across the United States. The urban-rural divide has been a major factor in U.S. elections for the past several decades and played an important role in President Trump’s reelection victory in 2024, when nearly seven in ten rural voters voted for him. As the 2026 midterm election approaches, the survey finds that while rural voters continue to lean Republican, concerns about the cost of living loom large, and disapproval of President Trump’s handling of the economy may be diminishing voter enthusiasm among some rural Republicans. At the same time, health care costs are also a top election issue for rural voters and an important component of their cost-of-living concerns. By more than a 2-1 margin, rural voters say the Trump administration’s health care policies have worsened their health care costs and access to care in their communities, while many express frustration with both political parties on health costs, saying they trust neither to deal with this issue. Rural voters’ economic sentiments have worsened in many respects since 2017, when KFF and the Washington Post explored similar subjects in a Survey of Rural America. These and other findings shed light on the mood and concerns of rural voters in the run-up to the 2026 midterms.

Explore KFF Health News and The Associated Press’ Reporting:

Economic frustration tests Trump’s standing with rural voters, new AP-KFF poll finds, Sept. 23, 2026

Rural MAHA Followers Say Trump Health Policies Haven’t Reached Their Communities, Sept. 30, 2026

NPR Morning Edition: Rural voters support MAHA movement, but feel little impact, poll finds, Sept. 30, 2026

Trump’s Immigration Crackdown Divides Rural Voters, KFF-AP Poll Finds, Oct. 5, 2026

News Release

KFF/AP Survey Probes Rural Voters’ Increasing Anxieties About the Rising Cost of Living, Including Health Costs, Heading into the Midterm Elections

Rural Voters are More Likely to Trust Republicans than Democrats to Tackle These Issues, But Economic Dissatisfaction May Dampen Turnout among Rural Republicans, and Trump’s Health Policies Are Viewed Negatively

Published: Sep 23, 2026

Rural voters’ frustrations about the cost of living in their community are growing and appear to be chipping away at Republicans’ enthusiasm to vote as the midterm elections near, a new KFF/Associated Press (AP) Survey of Rural Voters finds.

The survey of more than 2,000 rural voters probes the views and experiences of a group who have been strong supporters of President Trump and Republicans but are feeling economically stressed and facing higher health care costs. The project includes a polling analysis from KFF, which often partners with media organizations on surveys, and reporting from journalists at the AP and KFF Health News. Additional stories drawing on the poll findings and rural voters’ perspectives will come out in the coming weeks.

The survey’s key takeaways include:

  • Cost of living concerns are increasing, and Republicans maintain an edge with rural voters. Rural voters overwhelmingly name the cost of living as the top issue they want candidates to talk about, and three quarters now rate the cost of living in their area as either “fair” or “poor,” a 25-percentage point increase from 2017. When it comes to household expenses, rural voters worry most about health costs and gas prices. More rural voters prefer the Republican Party than the Democratic Party to best address the cost of living (40% v. 25%), though a quarter (27%), including most independents, trust neither party.
  • Economic frustration may hurt turnout among Republicans. Eight in ten rural Democrats say they’re “absolutely certain” to vote in the upcoming midterm, somewhat higher than the 74% of rural Republican voters who say so. This disparity appears to be at least partly a result of dissatisfaction with President Trump’s economic policies. Among the 27% of rural Republican voters who disapprove of President Trump’s handling of the economy, a smaller share (59%) say they are “absolutely certain” to vote.
  • Views of President Trump’s health care policies skew negative. Slightly more than half (54%) of rural voters disapprove of President Trump’s handling of health care and largely view his health care policies as having negatively rather than positively impacted their health care costs, Medicaid, and the availability of care where they live. Still, the Republican Party has a narrow advantage over the Democratic Party in rural voters’ trust to handle the cost of health care (33% vs. 28%), though three in ten (29%) trust neither party to deal with the issue.
  • Medicaid viewed as important, but messaging about fraud resonates with Republicans. The overwhelming majority (92%) of rural voters say Medicaid is important for people in their local community, and about half (49%) have had a personal or family connection to the program at some point in their lives. But messaging about fraud may appeal to rural Republican voters, as fraud in government programs is their top issue for candidates to talk about.

The survey also examines rural voters’ views about job opportunities and safety in their community, who they trust to handle key economic and health care issues, and health care access issues in their communities, including provider and hospital shortages.

METHODOLOGY

Designed and analyzed by public opinion researchers at KFF and the Associated Press, this survey was conducted August 12-24, 2026, online and by telephone among a nationally representative sample of 2,241 U.S. adults registered to vote in rural areas of the country. The margin of sampling error is plus or minus three percentage points for the full sample of rural voters. For results based on other subgroups, the margin of sampling error may be higher. The survey was conducted in English and Spanish.

About KFF

KFF is the independent source for health policy research, polling, and journalism. Its mission is to serve as a nonpartisan source of information for policymakers, the media, the health policy community, and the public. KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF.
About the Associated Press

The Associated Press is an independent global news organization dedicated to factual reporting. Founded in 1846, AP today remains the most trusted source of fast, accurate, unbiased news in all formats and the essential provider of the technology and services vital to the news business. More than half the world’s population sees AP journalism every day. Online: http://www.ap.org

The Trump Administration’s Foreign Aid Review: Status of the President’s Malaria Initiative (PMI)

Published: Sep 22, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on PMI

  • The U.S. government has been involved in global malaria activities since the 1950s and has been the largest donor to the sector. In 2005, the President’s Malaria Initiative (PMI) was launched to scale up funding and activities to address malaria in the hardest hit African countries, helping to contribute to global success in driving down malaria cases and deaths.
  • Still, in 2024, there were 282 million cases of malaria, a life-threatening disease spread to humans by mosquitoes, and 610,000 malaria deaths (the majority of which were among children under age five), a slight increase over the prior year.
  • Recent decades have seen major gains in reducing the impact of malaria, and PMI is credited with having helped to save 11.7 million lives and prevent 2.1 billion malaria cases. Indeed, as of 2024, in countries where PMI worked, global efforts supported a 29% decrease in malaria case rates and 48% decline in deaths. In addition, U.S. malaria assistance has been found to bolster the national economies in countries and communities most heavily affected by the disease with an analysis finding that every dollar of U.S. malaria assistance increased GDP in recipient countries nearly six-fold. The introduction of two malaria vaccines in 2021 and 2023 has increased optimism in the potential to further strengthen global malaria control.
  • Prior to the dissolution of USAID in 2025, PMI had operated as an interagency initiative led by USAID and implemented in partnership with CDC, focused in 30 countries that account for most of the world’s malaria cases and deaths. It had been overseen by a U.S. Global Malaria Coordinator, a position created by Congress in 2008 to be appointed by the President and based at USAID.
  • While the Trump administration has requested significantly less funding for PMI in its budget requests, prior to the start of the Trump administration U.S. funding provided to malaria control efforts and research activities was approximately $1 billion in FY 2024, including about $805 million to PMI and other bilateral global malaria efforts at the State Department and CDC; funding for the Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund) was $1.65 billion.

Current Status of PMI/Malaria Activities

The following administration actions have had a significant impact on PMI operations:

  • Stop-work order: The stop-work order initially froze all PMI programming and services, halting existing PMI activities, including bed net provision, residual spraying and delivery of antimalarial medicines. Because the order halted payments, many implementers had to terminate staff and end some services.
  • Limited waiver: Malaria programs received a limited waiver on February 4, 2025, allowing “life-saving services” to continue, including those that “must resume within 30 days to ensure malaria diagnosis and treatment, as well as prevention through distribution of nets and indoor residual spraying targeting highest burden areas…and lifesaving malaria medicines for pregnant women and children”. Even with the waiver, services remained disrupted and implementers faced challenges in getting permission to resume programming and difficulties in getting paid.
  • Dissolution of USAID: USAID was the main government implementing agency for malaria efforts, obligating almost all bilateral malaria assistance in FY 2023 (96%). Without USAID and most of its staff, PMI’s implementation capacity and operations have been affected. In addition, announcements of reductions at CDC could further affect global malaria efforts.
  • Canceled awards: In early 2025, it was reported that the administration canceled 86% of all USAID awards. KFF analysis found that of the 770 global health awards identified, 157 included malaria activities, 80% of which were terminated.
  • Legal actions: In response to two lawsuits filed against the administration’s actions, a federal judge issued a preliminary injunction ordering the government to pay for work completed by February 13, 2025, although not all payments have been made and the court did not stop the government from canceling awards. The government appealed the ruling and after several subsequent rulings in the case, the Supreme Court ultimately allowed the government to rescind (cancel) a portion of expiring global health funds before the end of the fiscal year. Further proceedings have been stayed, pending the outcome of a separate case.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and move any remaining USAID operations to the State Department, with global health activities, including for malaria, to be integrated into its Bureau of Global Health Security and Diplomacy (GHSD) which oversees PEPFAR. On May 29, 2025, the State Department further notified Congress of its proposed reorganization plan, and with the dissolution of USAID, programs moved in July 2025.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. Malaria has been included in most of the agreements signed to date, although there is little information available on activities and funding. A U.S. Malaria Coordinator has yet to be appointed.
  • Policy restrictions: In January 2025, the Trump administration reinstated the expanded Mexico City Policy from Trump’s first term and further expanded it in January 2026 to apply to almost all non-military foreign assistance, many more entities, and additional areas of restrictions including activities related to diversity, equity and inclusion and “gender ideology” under a broader umbrella known as the “Promoting Human Flourishing in Foreign Assistance” (PHFFA) Policy.
  • Funding: The Trump administration has requested significantly less funding for PMI and other malaria efforts in its budget requests and canceled funding for numerous malaria-related projects and awards. Despite this, Congress has continued to appropriate level funding for malaria control efforts and research activities, reaching approximately $1 billion in FY 2026 (including about $805 million for PMI and other bilateral global malaria efforts at the State Department and CDC). It also appropriated $1.25 billion for the Global Fund in FY 2026.

Impact on PMI Services and Outcomes

  • An internal USAID memo from 2025 estimated that an additional 12.5-17.9 million malaria cases and an additional 71,000-166,000 deaths could occur annually if PMI was halted permanently.
  • A rapid assessment survey of 108 WHO country offices in 2025 found that of the 64 malaria-endemic countries surveyed, more than half reported moderate or severe disruptions to malaria services, including for medicines and health products, due to the U.S. foreign aid freeze and other shortages.
  • In early April 2025, almost 30% of planned insecticide treated net (ITN) distribution campaigns were off-track or at risk of being delayed due to funding shortages, and such risks continue today. Several countries also face stock-out risks for key commodities including for rapid diagnostic tests (RDTs) and artemisinin-based combination therapy (ACT). Reductions in funding also threaten investments in new and improved malaria prevention, diagnostic, and treatment interventions. Such disruptions pose significant risks, particularly during peak malaria seasons across Africa where seasonal malaria campaigns are needed to protect millions of people. In a court filing challenging the funding freeze, for example, a major U.S. implementer reported that it had to delay the start of anti-malarial campaigns in Africa last year.
  • A modeling project estimated that a full year U.S. funding cuts could result in an additional 2.4 million malaria cases among adults and an additional 7.2 million malaria cases among children.

What to Watch

  • Implementation of the America First Global Health Strategy multi-year agreements with countries
  • Status of U.S. funding appropriated by Congress for bilateral malaria efforts and contributions to the Global Fund
  • Impact of the PHFFA Policy on U.S. funding and programs
  • Impact of U.S. changes to global health programs on health outcomes

The Trump Administration’s Foreign Aid Review: Status of U.S. Global Maternal and Child Health Efforts

Published: Sep 22, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on U.S. Global Maternal and Child Health (MCH) Efforts

  • The U.S. government has been involved in supporting global maternal and child health (MCH) efforts for more than 50 years, as a top donor and provider of technical assistance and other support, helping to contribute to worldwide success in reducing maternal and child mortality.
  • Still, in 2024, 4.9 million children under the age of 5 (more than 13,000 every day) died, with the highest rates of under-5 mortality in sub-Saharan Africa. About 260,000 women (or nearly one every two minutes) died during and following pregnancy and childbirth in 2023 – 92% of them in low- and middle-income countries. The majority of these deaths are preventable with proper interventions and access to care.
  • Recent decades have seen major gains in preventing maternal and child mortality. Both the number and the rate of children dying before age 5 have fallen by more than 60% since 1990, and almost 100 countries have cut under-five mortality rates by at least two-thirds in that time. From 2000 to 2023, the annual number of maternal deaths worldwide fell by 40%. The U.S. government has contributed significantly to these gains, reporting that it helped to save the lives of more than 9.3 million children and 340,000 women over the past decade alone.
  • Prior to its dissolution in 2025, USAID had served as the lead U.S. implementing agency for MCH activities, reaching more than 40 countries, including 25 “high priority” countries, primarily in Africa and southern Asia. The CDC also supported global MCH activities, primarily through immunization and technical assistance to build in-country capacity.
  • Prior to the start of the Trump administration, U.S. funding provided to MCH activities was approximately $1.31 billion in FY 2024, including $865.7 million for bilateral MCH activities, $300 million for Gavi and $142 million for UNICEF.

Current Status of U.S. MCH Programs

The following administration actions have had a significant impact on MCH program operations:

  • Stop-work order: The stop-work order initially froze all MCH programming and services, halting USAID’s MCH programming, including pre- and post-natal health services and lifesaving maternal health care. Because the order halted payments, many implementers had to terminate staff and end some services.
  • Limited waiver: Maternal and child health activities were included in a limited waiver issued by the State Department on February 4, 2025, allowing “life-saving services” to continue, defined as essential services related to the prevention, diagnosis and treatment of severe illnesses and conditions which–if not addressed–lead to mortality in women, newborns, and children under five. Listed in the waiver were antenatal care and post-partum services, essential newborn care, essential immunizations and treatment of acute child illness. Even with the waiver, services remained disrupted and implementers faced challenges in getting permission to resume programming and difficulties in getting paid.
  • Dissolution of USAID: As the main government implementer of MCH efforts, the dissolution of USAID and loss of most staff significantly affected MCH implementation capacity and operations. In addition, announcements of reductions at CDC could further affect global MCH efforts.
  • Canceled awards: In early 2025, it was reported that the administration canceled 86% of all USAID awards. KFF analysis found that of the 770 global health awards identified, 266 included MCH activities, 86% of which were terminated.
  • Legal actions: In response to two lawsuits filed against the administration’s actions, a federal judge issued a preliminary injunction ordering the government to pay for work completed by February 13, 2025, although not all payments have been made and the court did not stop the government from canceling awards. The government appealed the ruling and after several subsequent rulings in the case, the Supreme Court ultimately allowed the government to rescind (cancel) a portion of expiring global health funds before the end of the fiscal year. Further proceedings have been stayed, pending the outcome of a separate case.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and move any remaining USAID operations to the State Department, with global health activities, including for MCH, to be integrated into its Bureau of Global Health Security and Diplomacy (GHSD) which oversees PEPFAR. On May 29, 2025, the State Department further notified Congress of its proposed reorganization plan, and with the dissolution of USAID, programs moved in July 2025.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. MCH has been included in several of the agreements signed to date, although there is little information available on activities and funding.
  • Policy restrictions: In January 2025,the Trump administration reinstated the expanded Mexico City Policy from Trump’s first term and further expanded it in January 2026 to apply to almost all non-military foreign assistance, many more entities, and additional areas of restrictions including activities related to diversity, equity and inclusion and “gender ideology” under a broader umbrella known as the “Promoting Human Flourishing in Foreign Assistance” (PHFFA) Policy.
  • Funding: The Trump administration has requested significantly less funding for MCH in its budget requests and canceled or suspended funding for numerous MCH-related projects and awards. This includes rescinding funding for UNICEF; the administration also suspended funding for Gavi unless it met certain conditions (in July 2026 it announced that the withheld funds would be released following discussions with Gavi, and funding has since been provided to the organization). Despite this, Congress has continued to appropriate level funding for these programs, totaling approximately $1.29 billion in FY 2026 (including $845 million for bilateral MCH activities at the State Department and CDC, $300 million for Gavi, and funding for UNICEF “consistent with prior year levels”).

Impact on MCH Services and Outcomes

  • An internal USAID memo from 2025 reported that the cessation of USAID programming for MCH would affect services for 16.8 million pregnant women annually, eliminate postnatal care for 11.3 million newborns within the first two days of life, and prevent 14.8 million children under 5 from receiving treatment for pneumonia and diarrhea.
  • A rapid assessment survey of 108 WHO country offices in 2025 found that almost half reported moderate or severe disruptions to MCH services, including for medicines and health products, due to the U.S. foreign aid freeze and other shortages. WHO also said that funding cuts have “led to facility closures and loss of health workers, while also disrupting supply chains for lifesaving supplies and medicines such as treatments for haemorrhage, pre-eclampsia and malaria – all leading causes of maternal deaths.”
  • In addition, several modeling studies have found that cuts in or termination of U.S. MCH funding could result in significant increases in maternal and child deaths and, as a result, the maternal mortality ratio, under 5 mortality rate, and stillbirth rate in coming years.

What to Watch

  • Implementation of the America First Global Health Strategy multi-year agreements with countries
  • Status of U.S. funding appropriated by Congress for bilateral MCH efforts and contributions to Gavi and UNICEF
  • Impact of the PHFFA Policy on U.S. funding and programs
  • Impact of U.S. changes to global health programs on health outcomes

Implementation of Medicaid Immigrant Eligibility Restrictions Under the 2025 Reconciliation Law: Issues to Consider

Published: Sep 22, 2026

Introduction

The 2025 reconciliation law includes new eligibility restrictions for many lawfully present immigrants for federally-funded health programs, including Medicaid and the Children’s Health Insurance Program (CHIP), subsidized Affordable Care Act (ACA) Marketplace, and Medicare coverage. The eligibility restrictions for Medicaid and CHIP become effective October 1, 2026. These restrictions will eliminate eligibility for many groups of lawfully present immigrants, including refugees and asylees without a green card, among others. Under longstanding federal policy, undocumented immigrants already are ineligible for federally funded health coverage. The Congressional Budget Office (CBO) estimates that eligibility restrictions in Medicaid or CHIP will reduce federal spending by $6.2 billion and lead to an additional 100,000 individuals becoming uninsured by 2034.

The Centers for Medicare & Medicaid Services (CMS) released guidance and an implementation toolkit for states to implement the eligibility changes. Beyond those losing coverage because they are no longer eligible, there may also be coverage losses among individuals who remain eligible due to administrative barriers, particularly if they have challenges understanding or responding to notices requesting information and documentation. States will also face increased administrative burdens to implement the changes. This brief provides an overview of implementation of the immigrant eligibility changes and issues to consider for affected individuals and states.

Medicaid Immigrant Eligibility Changes

Starting October 1, 2026, the 2025 reconciliation law will restrict Medicaid and CHIP eligibility to lawful permanent residents (LPRs or “green card” holders), Cuban and Haitian entrants, people residing in the U.S. under Compacts of Free Association (COFA), and lawfully residing children and pregnant immigrants in states that cover them under the Medicaid and/or CHIP option (Table 1). The law will eliminate eligibility for many other groups of lawfully present immigrants, including refugees and asylees without a green card, among others. Prior to the 2025 reconciliation law, undocumented immigrants were already ineligible for Medicaid and CHIP. Additionally, the 1996 Personal Responsibility and Work Opportunity Reconciliation Act (PRWORA) limited Medicaid and CHIP eligibility to certain groups of lawfully present immigrants deemed to have a “qualified status” and required many of these groups to wait at least five years before they could enroll even if they met other eligibility criteria. The 2025 reconciliation law does not change the application of PRWORA. Under PRWORA, LPRs are generally subject to the five-year waiting period subject to some exceptions. Cuban and Haitian entrants and COFA migrants are exempt from the waiting period.

States will continue to have the option to provide coverage to lawfully residing children and pregnant people without a five-year wait under the Immigrant Children’s Health Improvement Act (ICHIA) option (also referred to as the CHIPRA 214 option). They will also continue to have the option to provide prenatal care and pregnancy related benefits to targeted low-income children beginning from conception to end of pregnancy (FCEP) regardless of their parent’s immigration status.

Emergency Medicaid and CHIP Health Services Initiative expenditures also are exempt from the new immigrant eligibility restrictions. Emergency Medicaid reimburses hospitals for emergency care they are obligated to provide to individuals who meet other Medicaid eligibility requirements (such as income), but who do not have an eligible immigration status, including undocumented immigrants and lawfully present immigrants who are not eligible for Medicaid or CHIP. CHIP Health Services Initiatives allow states to use a limited portion of CHIP funding to implement public health services aimed at improving the health of low-income children.

Eligible Immigration Statuses for Medicaid and CHIP (Table)

Implementation of Immigrant Eligibility Changes

States must redetermine eligibility for all “potentially affected” existing Medicaid enrollees under the new rules by October 1, 2026, and conduct new eligibility determinations consistent with the new rules beginning October 1, 2026. CMS describes potentially affected beneficiaries as those receiving full Medicaid or CHIP benefits who do not have an eligible immigration status under the new rules. CMS indicates that because states vary in the information they keep on file for enrollees, they may have differing ability to identify potentially affected enrollees. As such, some states may need to reverify eligibility for a broader group of noncitizen enrollees.

For potentially affected enrollees, states must first attempt to reverify satisfactory immigration status under the new rules through existing information and automated data matches before contacting the enrollee. States will seek to verify immigration status through the Department of Homeland Security’s (DHS) Systematic Alien Verification for Entitlements (SAVE) program and using Social Security Administration (SSA) databases. If the state verifies satisfactory immigration status, including eligibility under the option for lawfully residing immigrant children or pregnant people, the enrollee will maintain full coverage and should be notified by the state. However, CMS notes that SAVE provides “point in time” verification and does not update past SAVE verification responses when there is a change in immigration status or category. As such, potentially affected beneficiaries may have applied for and been granted adjustment of status to that of an LPR or may have another qualifying immigration status or category that is not reflected in SAVE.

If the state is unable to verify satisfactory immigration status through existing information and data matches, it must request additional information from the enrollee and give the enrollee a reasonable period of time to respond. If the enrollee responds and declares citizenship or a satisfactory immigration status but the state is still unable to verify this information through the SAVE database, the state must provide the enrollee with a 90-day reasonable opportunity period to verify status, during which the state must continue to provide coverage, which may extend beyond October 1, 2026. If the enrollee provides documentation of satisfactory immigration status which is verified with SAVE, the enrollee will retain coverage and should be notified by the state. If the enrollee provides information or documentation that indicates they do not have a satisfactory immigration status or if they do not respond within the specified timeframe, the state must consider whether the enrollee is eligible under the option to cover lawfully residing immigrant children and/or pregnant people (if the state has elected the option), if the enrollee remains eligible for Emergency Medicaid, or if the enrollee is no longer eligible for any coverage. After this determination, the state must provide advance notice, including the right to a Medicaid fair hearing or CHIP review, before terminating coverage or reducing benefits for the enrollee. For Medicaid, states must provide at least ten days advance notice, and, for CHIP, states must provide timely and adequate written notice of the proposed termination and an opportunity for review.

States must update eligibility systems and financial claiming and enrollment data reporting to be consistent with the new eligibility rules. CMS indicates that states must ensure appropriate claiming for individuals eligible only for Emergency Medicaid. It also indicates that they must ensure systems can identify and isolate costs, including administrative costs, related to state-only funded health programs for immigrants so that they do not claim federal matching funds for that coverage. CMS notes that if states cannot make changes to comply with the law, they risk losing federal financial participation (FFP) for Medicaid claims. CMS notes that states may also need to make updates to other materials including Medicaid application and renewal forms; notices to applicants and enrollees; outreach communications to applicants, enrollees, and community-based organizations; and call center scripts, automated messages, and worker guidance. CMS also notes that states should update all presumptive eligibility applications and train providers and caseworkers to correctly assess presumptive eligibility under the new rules. States use presumptive eligibility to expedite Medicaid enrollment for children and pregnant people to access care while their regular application is being processed.

Issues to Consider

Individuals no longer eligible for Medicaid under the new rules will be disenrolled from coverage and left with limited comprehensive coverage options. Individuals in Medicaid may still qualify for Emergency Medicaid but will only be covered for emergency services. Lawfully residing immigrant children and pregnant people will be able to maintain coverage in states that have adopted this option, but coverage varies by state. Subsidized ACA Marketplace coverage will also be limited to lawfully present immigrants who are LPRs, Cuban and Haitian entrants, and people residing in the U.S. under COFA beginning January 1, 2027. Other lawfully present immigrants would be eligible to purchase Marketplace coverage at full cost, but it would likely be unaffordable. Individuals who lose coverage may utilize community health centers for free or sliding-fee scale health care services, but they may have access to a limited scope of services. Some states may provide fully state-funded coverage to those losing Medicaid coverage. However, several states have recently scaled back state-funded coverage programs for immigrants or have reached enrollment caps due to budget pressures and higher than expected demand.

Individuals who remain eligible for Medicaid may experience procedural disenrollments or coverage disruptions due to fear, confusion, or challenges completing verification requirements. Individuals may have difficulty understanding new eligibility rules and whether they remain eligible. Confusion and fears about enrolling in coverage may be amplified by other immigration policies like public charge, new agreements for CMS to share Medicaid data with DHS and Immigration and Customs Enforcement (ICE), and other increased federal immigration enforcement actions. Eligible enrollees may also face challenges submitting required documentation to verify immigration status.

Adequate and accessible outreach, information, and assistance will be key for preventing potential administrative coverage losses. CMS encourages states to use robust, clear, and consistent outreach and communication strategies to help enrollees and applicants understand the upcoming Medicaid eligibility changes and prepare for redetermination and renewals. CMS also suggests that states emphasize notices are time-sensitive, such as by labeling envelopes as such. Outreach through trusted, community-based organizations can help boost awareness among those who will be affected, and community partners may be able to help individuals consider alternatives, including how to access free or low-cost care. Additionally, ensuring linguistic access to information and notices will be key for individuals with limited English proficiency.

Comprehensive information on notices provided to enrollees about Medicaid immigrant eligibility changes is not publicly available across states, but KFF analysis of notices collected from 16 states illustrates there is variation in the information they provide and their accessibility. Most of the examined notices list which groups of lawfully present immigrants remain eligible for coverage, but fewer identify the groups losing coverage. Some states, such as California and Oregon, are transitioning immigrants losing federally funded coverage to state-funded coverage so they include language about how coverage is changing versus potential disenrollment. The examined notices also vary in the information and options provided to enrollees to verify immigration status. Some provide specific lists of acceptable documentation while others request proof of status without identifying specific documentation or direct enrollees to a website or other contact to identify acceptable documentation. Most examined notices offer multiple pathways for enrollees to submit proof of immigration status, including through online accounts or websites, mail, fax, phone, or in-person, while some offer more limited options such as in-person or mail only. The examined notices also vary in the extent to which they advise enrollees about other potential coverage sources, including Emergency Medicaid, and the types of assistance they highlight for enrollees, with some highlighting assisters or legal service organizations as resources. Among the examined notices, only a few were available in another language and/or provided taglines in other languages. However, states may have additional in-language resources that they are providing directly to enrollees that were not publicly available. Reading literacy levels also varied substantially across the examined notices, from a fourth-grade level to a tenth-grade level, as assessed using the SMOG readability calculator, a formula commonly used to evaluate the readability of health-related materials.  

States will face increased administrative burden to conduct outreach, reverify enrollees, and update systems and other materials to reflect new immigrant eligibility rules amid implementation of other Medicaid changes included in the 2025 reconciliation law. States are implementing the immigrant eligibility changes at the same time they are implementing Medicaid work requirements and more frequent eligibility redeterminations for ACA expansion adults. Implementing these changes on a short timeline will increase administrative burdens for states and require state budget investments. States may also make additional investments to expand outreach and to hire and train workers. Enhanced funding is available to support technology systems costs, with a 90% federal match available for design, development, and installation activities and a 75% match available for ongoing operations of CMS approved systems. However, at the same time, states are facing reductions in federal Medicaid funds due to broader changes in the reconciliation law and tightening fiscal conditions due to slowing revenue growth. With regard specifically to immigrants, the law reduces the federal Medicaid matching rate provided to states for Emergency Medicaid services provided to expansion adults who would otherwise be eligible for Medicaid except for their immigration status to the regular matching rate starting October 1, 2026.

States have limited federal guidance to implement the new eligibility rules among certain groups of noncitizens. CMS indicated that it would provide additional guidance related to eligibility changes for individuals enrolled in both Medicare and Medicaid, referred to as dual-eligible individuals, as Medicare immigrant eligibility will be restricted on a different timeline than Medicaid. However, this guidance is not yet available, creating uncertainty for states regarding how Medicaid eligibility changes may interact with Medicare enrollment and cost-sharing assistance for affected individuals. Additionally, many states will need to verify eligibility among noncitizens who are automatically enrolled in Medicaid through Supplemental Security Income (SSI) approval. SSI is a means-tested federal program administered by the SSA that pays monthly cash assistance to people who are unable to work because of a disability and generally qualifies people to receive health coverage through Medicaid, which may be their only source of coverage for long-term services and supports and disability-related services. The 2025 reconciliation law does not change immigrant eligibility rules for SSI, but some immigrants will lose their Medicaid coverage. CMS notes that guidance on the changes the SSA is making to the State Data Exchange (SDX) file to identify eligible noncitizen SSI recipients is forthcoming, but it has not yet been made available.

States may face additional uncertainties due to a lack of CMS guidance. CMS is updating the Transformed-Medicaid Statistical Information System (T-MSIS) Data Guide and plans to provide additional information on T-MSIS data reporting in forthcoming guidance. However, states do not yet have final guidance on how T-MSIS enrollment data submissions will specify enrollee immigration status. CMS also requires all states to submit updated State Plan Amendments (SPAs) with new immigrant eligibility restrictions by December 31, 2026, but has only indicated revised Medicaid and CHIP SPA templates will be forthcoming. Likewise, CMS plans to provide additional technical assistance to states about the potential impact for currently approved Section 1115 waiver demonstrations. CMS also directs states with Medicaid Managed Care programs to evaluate whether the immigrant eligibility changes require capitation rate adjustments or amended rate certifications based on guidance released in September 2025, leaving some actuarial judgments to the states. States will also need to utilize a separate and distinct contract and payment system with any managed care plan they contract with to provide state-funded health coverage services, which may be subject to CMS scrutiny.

The Business of Health with Chip Kahn

AI: To Regulate, or Not to Regulate?

September 22, 2026

Video

Audio

About this Episode


Episode 16, AI Series: Across the tech industry, many of AI’s own leaders are calling for oversight — self-imposed or from government. That debate is on, but where it will land is anyone’s guess. Joe Grogan takes a different tack: the biggest threat in health care AI may not be too little regulation, but the wrong kind. And he has seen regulation from the seats where it gets made: the White House Domestic Policy Council, the federal health care budget at OMB, and before Washington, the industry side of bringing a cure for Hepatitis C to patients. Chip and Grogan discuss the federal government’s proper role in regulating generative AI, the growing patchwork of state AI laws, why CMS reimbursement structures need to change, and how Europe’s cautious approach is impeding the technology’s growth. Grogan closes with his two biggest worries: fear-driven policy that bans innovation outright, and the risk to patients’ most sensitive data as AI’s appetite for it grows.

The Host


Headshot photo of Chip Kahn wearing a navy blue suit with a red tie, red pendant on lapel, and glasses.

Sr. Visiting Fellow

Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.
Guest


Chairman of the Board, Paragon Health Institute; former Director, White House Domestic Policy Council

Joe Grogan is a health care expert with a unique blend of private sector and government experience spanning over two decades. In addition to serving as the Chairman of the Board and Public Advisor at the Paragon Health Institute, Grogan is serving currently as a Senior Fellow at the Leonard D. Schaeffer Center for Health Policy and Economics at the University of Southern California.

Prior to serving in the West Wing as Domestic Policy Advisor, he was Associate Director for Health Policy at the Office of Management and Budget. In government, he also served as Special Assistant to the FDA Commissioner and as Executive Director of the Presidential Advisory Council on HIV/AIDS (PACHA) during the George W. Bush administration.

He holds a bachelor’s degree from State University of New York at Albany and a law degree from the College of William and Mary.


SERIES

This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.

The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.

What We Know from the Latest PEPFAR Data: Analysis of FY 2025 Quarter 4 Results

Authors: Jennifer Kates, Anna Rouw, and Allyala Nandakumar
Published: Sep 21, 2026

Editorial Note: Originally published on April 23, 2026, this analysis has been updated to present data on the number of HIV-exposed infants tested for HIV within the first 12 months of life, rather than the number of HIV-positive infants with a diagnostic sample collected within the first 12 months of life.

Since the start of the second Trump administration, the President’s Emergency Plan for AIDS Relief (PEPFAR), the U.S. global HIV/AIDS program credited with saving 26 million lives, has undergone significant changes and disruptions as part of a broader foreign aid review. Recent changes include: a temporary stop work order and eventual limits to what services could be continued; the cancellation of numerous PEPFAR awards; and a reorganization of U.S. global health programs, including the launch of a new “America First Global Health Strategy” which is anchored to bilateral agreements with countries, a focus on frontline commodities and services, and a shift from disease-specific programming to a more integrated approach. While modeling estimates and field surveys have provided some information about the potential impact of these changes and disruptions, there has been limited data available for such assessments. PEPFAR’s flagship data platform has historically posted financial and program level results, including from PEPFAR’s Monitoring, Evaluation, and Reporting (MER) system (MER was launched more than a decade ago). However, the data platform was temporarily removed in early 2025 and, when restored, it did not include any program data from FY 2025.   

On April 17, 2026, the State Department released Fiscal Year (FY) 2025 fourth quarter (Q4) MER data (covering the July 1 to September 30, 2025 period), providing the first program-level data made available since the changes of last year. Data for quarters 1-3 were not released, which, per the State Department, is due to data reporting and implementation challenges due to the changes. To provide a snapshot of PEPFAR results after these changes, and given this limitation, this analysis compares PEPFAR’s FY 2025 Q4 results to Q4 results from the previous four fiscal years for a subset of MER indicators. By comparing the same time period for each fiscal year, this approach helps to capture seasonal or other reporting fluctuations that could occur. However, it does not allow for an assessment of disruptions or other changes that may have occurred for the full FY 2025 period.1

While these data are limited (see box on methodology and data limitations) and provide only a snapshot view, they nevertheless provide insights into understanding how PEPFAR is performing following changes by the Trump administration. Overall, the data show that for some indicators, progress  declined in FY 2025 Q4, including support for prevention services such as pre-exposure prophylaxis (PrEP) and the DREAMS program for adolescent girls and young women, both of which were significantly scaled back by the administration. Reduced access to prevention could lead to increases in new HIV infections in the future. There was also a drop in the number of people with HIV newly enrolled on antiretroviral therapy (ART), an important measure of access. At the same time, without more complete data, there is ambiguity in some of the indicators. For example, both the number of HIV tests conducted and the number testing positive for HIV fell, which could represent an actual decline in new infections or simply a decline in access to testing. Finally, there are areas where progress has been maintained or potentially improved, including the total number of people with HIV on ART, which was stable, and an increase in the number of people living with both HIV and TB who are receiving ART. Going forward, the future of transparent PEPFAR data monitoring and reporting remains uncertain, as it’s unclear whether or not these data updates will continue to be provided given the shift in the U.S. global health strategy to country governments and from disease-specific programming to a more integrated approach.  Without such data, it will be difficult to understand the implications and outcomes of these significant changes. 

Findings

PEPFAR’s Q4 treatment results over the period were mixed. While there were some stable results, particularly for the number of people receiving ART, others dropped, such as those newly enrolled on ART.

  • The number of individuals with HIV on antiretroviral therapy (ART) remained relatively stable in FY 2025 Q4 compared to FY 2024 Q4 (20.3 million2 compared to 20.4 million) and was higher than the prior fiscal years.
  • At the same time, the number newly enrolled on ART in FY 2025 Q4 was the lowest over the period, including 16% lower than FY 2024 Q4 (389.1K compared to 463.5K). This is part of a broader decline over the past five years but one of the steepest year-to-year quarter declines.
  • Similarly, the number of pregnant women testing positive for HIV and receiving ART in FY 2025 Q4 was also the lowest over the period, including a 14% decline compared to FY 2024 Q4 (189.3K compared to 220.7K).   
  • Finally, individuals on ART with documented viral load suppression (VLS) declined in FY 2025 Q4 by 7% compared to FY 2024 Q4 (14.6 million compared to 15.8 million), but was higher than the prior fiscal years.
Treatment: Individuals on ART, FY 2021 - FY 2025 (Column Chart)

HIV testing and diagnostic results were mixed in FY 2025 Q4 compared to FY 2024 Q4, although there were fluctuations over the five-year period.

  • Both the number of individuals tested for HIV and the number testing positive fell. The number of individuals tested fell by 17% in FY 2025 Q4 compared to FY 2024 Q4 (19.6 million compared to 23.7 million), though was still higher than in prior years. The number testing positive similarly fell by 15% in FY 2025 Q4 compared to FY 2024 Q4 (380.2K compared to 449.8K), continuing a downward decline and reaching the lowest number over the period.
  • Despite these drops, the number of pregnant women attending antenatal care who know their HIV status in FY 2025 Q4 was highest over the period, including a 10% increase compared to FY 2024 Q4 (3.9 million compared to 3.6 million).
  • In addition, the number of HIV-exposed infants tested for HIV within the first year decreased in FY 2025 Q4 compared to FY 2024 Q4 (135,000 compared to 162,000) and was the lowest in recent years.
Testing: Individuals Tested for HIV, FY 2021 - FY 2025 (Column Chart)

Key PEPFAR prevention results saw large declines, including for PrEP.

  • The number of individuals who newly initiated PrEP declined by 41% in FY 2025 Q4 compared to FY 2024 Q4 (388K compared to 659.4K), falling to FY 2022 levels. Access to PrEP with PEPFAR support had increased steadily in recent years, before this drop.
  • Also declining significantly was the number of adolescent girls and young women (AGYW) who completed the DREAMS package of prevention services in FY 2025 Q4 compared to FY 2024 Q4 (a drop of 86%, from 1.9 million to 253.4k), its lowest level over the period and less than a quarter of those served in the prior years analyzed. DREAMS had been a major PEPFAR initiative to address the drivers of high HIV incidence rates among AGYW, including gender-based violence, gender inequality, poverty, and inadequate access to education. These broader services are no longer being prioritized by PEPFAR.
  • Similarly, the number of children and family members served by the Orphans and Vulnerable Children (OVC) program declined significantly in FY 2025 Q4 compared to FY 2024 Q4 (1.7 million compared to 6.5 million), falling to its lowest level in the last five years, and less than a quarter of those served in Q4 of 2022.
  • PEPFAR eliminated reporting on key and priority populations (those who were marginalized or faced particular barriers to HIV services, including men who have sex with men, people in prison, displaced persons or mobile communities, and others) reached with prevention and other interventions. Reporting on voluntary medical male circumcision (VMMC) was also eliminated.
Prevention: Individuals Newly on PrEP, FY 2021 - FY 2025 (Column Chart)

PEPFAR has also provided significant support to address HIV and TB co-infection, and risk of TB among those with HIV. These results were varied.

  • The number of individuals living with HIV who know their TB status slightly declined in FY 2025 Q4 compared to FY 2024 Q4 (199k compared to 208.7k) but was higher than prior years.
  • The number of individuals living with HIV and TB who are receiving ART declined considerably in FY 2025 Q4, compared to previous fiscal years, including a 33% drop compared to FY 2024 (138.9k compared to 208.1k).
  • Similarly, the number of individuals receiving ART who initiated TB prevention therapy declined in FY 2025 Q4 (467.7k compared to 823k), reaching its lowest level over the period and continuing a declining trend. The number for FY 2025 Q4 was a third of the number in FY 2021.
  • At the same time, the number of individuals receiving ART who initiated TB treatment increased in FY 2025 Q4 compared to FY 2024 Q4, to its highest level over the period.  
TB: People Living with HIV Who Know Their TB Status, FY 2021 - FY 2025 (Column Chart)

PEPFAR has, for many years, also worked to address the elevated risk of cervical cancer among women living with HIV. While screening for cervical cancer declined, the share receiving treatment for cervical cancer held steady.

  • The number of women living with HIV and receiving ART who were screened for cervical cancer declined in FY 2025 Q4 compared to FY 2024 Q4 (806.4K compared to 1.4 million), its lowest level over the period.
  • Of the women living with HIV and receiving ART and screened positive for cervical cancer, the share receiving treatment was only slightly below the prior period (89% in FY 2025 Q4 compared to 92% in FY 2024 Q4).
Cervical Cancer: Women on ART Screened for Cervical Cancer, FY 2021 - FY 2025 (Column Chart)
Select PEPFAR Indicators, FY 2021 - FY 2025 (Table)

Methods and Data Limitations

Data represent KFF and Boston University analysis of PEPFAR monitoring, evaluation and reporting (MER) datasets from the PEPFAR Panorama Spotlight for quarter 4 of fiscal years 2021-2025, with a particular focus on changes between FY 2024 and FY 2025 (all countries that reported data in FY 2024 Q4 also reported data in FY 2025 Q4). Data were accessed on April 17, 2026.   

Reporting for several indicators included in this analysis was changed from “required” to “optional” at some point for FY 2025 (current and prior reference guides for MER reporting can be found here). These indicators include:

  • Adolescent girls and young women completing DREAMS (AGYW_PREV)
  • Children and family members served by the OVC program (OVC_SERV)
  • Individuals with TB and HIV receiving ART (TB_ART)
  • Individuals on ART who initiated TB preventive therapy (TB_PREV)
  • Women on ART screened for cervical cancer (CXCA_SCRN)
  • Percentage of women on ART who screened positive for cervical cancer receiving treatment (CXCA_TX)

Because of these reporting requirement changes, declines in the data may reflect actual declines in services, or reduced reporting since participants are no longer required to track these metrics.

Jen Kates and Anna Rouw are with KFF. Allyala Nandakumar is with Boston University.

  1. One recent analysis, submitted for publication, attempts to address some of these issues by looking at reporting continuity across facilities over time. See, Honermann B, Grimsrud A, Lankiewicz E, Sherwood J, Millett G, The impact of the United States foreign aid freeze on HIV service delivery in PEPFAR-supported countries: a facility-level analysis of 2024–2025 programme data, https://www.medrxiv.org/content/10.64898/2026.04.17.26351143v1. ↩︎
  2. The number of individuals on ART in FY 2025 Q4 in the publicly available dataset is 20.3 million. The State Department’s press release about the data cites 20.6 million people. ↩︎