The Trump Administration’s Foreign Aid Review: Status of Global Health Security/Pandemic Preparedness

Published: Aug 6, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on U.S. Global Health Security Efforts

  • The U.S. has supported global health security (GHS) and pandemic preparedness efforts for decades through funding and technical support provided to low- and middle-income countries (as well as support for multilateral efforts). This had included the development of formal GHS partnerships with other countries, starting with 17 in 2014 and rising to more than 50 in 2024.
  • GHS efforts are designed to help countries and regions build capacities needed to prevent avoidable outbreaks, detect infectious disease threats early, and reduce the impacts of epidemics and pandemics through rapid and effective responses.
  • Specific activities include: improving surveillance and laboratory systems, reducing the risks of animal to human disease exposures, training epidemiologists, and fostering better biosafety and biosecurity practices.
  • U.S. investments in GHS have led to measurable increases in capacity, including improvement in 9 of 15 technical areas between 2018 and 2023 in GHS partnership countries and reductions in average outbreak response times.
  • Prior to 2025, multiple U.S. agencies, coordinated by the National Security Council (NSC), were involved in these efforts including USAID (now dissolved), the Centers for Disease Control and Prevention (CDC), the Department of Defense (DoD), the State Department, HHS, and USDA. The first U.S. GHS Strategy was released in 2019 by the first Trump administration and an updated strategy was released by the Biden administration in 2024.
  • Prior to the start of the Trump administration, U.S. funding provided to bilateral GHS activities in FY 2024 was $1.25 billion; $100 million was provided to the Coalition for Epidemic Preparedness Innovations (CEPI) and $250 million to the Pandemic Fund.

Current Status of U.S. Global Health Security Programs

The following administration actions have had a significant impact on U.S. GHS programs:

  • Stop-work order: The stop-work order initially froze all USAID-based GHS programming and services. As a result, many GHS implementing partners let staff go and some USAID-supported GHS activities in progress were interrupted, such as funding for transport of samples and phone plans for contact tracers.
  • Limited waiver: Some GHS activities were included in a limited waiver issued by the State Department on February 4 allowing “life-saving services” to continue, including: rapid emergency response to immediate infectious disease outbreaks, focused on pathogens with pandemic potential and those that pose a national security risk to U.S. citizens (e.g., mpox and H5N1), including detection, prevention, and containment and supply of medical countermeasures. Even with the waiver, services remained disrupted and implementers faced challenges in getting permission to resume programming and difficulties in getting paid.
  • Dissolution of USAID: Before its dissolution, USAID had about 50 staff supporting international outbreak response efforts, a number which dropped to six in the early weeks of the Trump administration. As a result, many GHS partners lost points of contact and technical support, in addition to the loss of funding. Announcements of reductions at the CDC could further affect GHS capacity.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and that any remaining USAID operations would be absorbed by the State Department with global health activities (including for GHS) to be integrated into its Bureau of Global Health Security and Diplomacy (GHSD). On May 29, 2025, the State Department further notified Congress of its proposed reorganization plan, and with the dissolution of USAID, programs moved in July 2025.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement (the Trump administration withdrew the 2024 Global Health Security Strategy and has not released an updated strategy). Per the America First strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. Global health security figures prominently in the new strategy and is part of all of the agreements signed to date. Goals include enabling detection of outbreaks with epidemic potential within seven days and containing outbreaks originating outside the U.S. rapidly at their source, prioritizing mobilization within 72 hours of detection.
  • Withdrawal from WHO: In January 2025, President Trump announced that the U.S. would withdraw from the World Health Organization (WHO) and halted its funding (the formal withdrawal was completed in January 2026). The administration also said that the U.S. would not be bound by the recently revised International Health Regulations or the new pandemic agreement being negotiated by WHO, two international instruments that outline roles and responsibilities for countries to prepare for and respond to outbreaks.
  • Funding: The Trump administration has requested significantly less funding for GHS in its budget requests and canceled or suspended funding for GHS-related projects and awards, including for contributions to CEPI and the Pandemic Fund. Despite this, Congress has continued to appropriate funding for bilateral GHS efforts at close to prior year levels, including $1.1 billion in FY 2026, and called for funding consistent with prior amounts for contributions to CEPI and the Pandemic Fund.

Impact on GHS Services and Outcomes

  • The combination of administration actions described above has reduced capacity and may challenge communication and coordination across U.S. agencies and with partners, contributing to slower responses to emerging health threats, greater impacts, and increased risk of importation of diseases into the U.S.
  • Experts estimate that there is a 50% chance of another pandemic emerging in the next 25 years, with the risk greatest in the least prepared countries. 
  • The health impacts of poorly controlled outbreaks can be severe. An internal USAID memo from 2025 estimated that the risk of losing USAID GHS programs alone could result in more than 28,000 new cases of dangerous infectious diseases, such as Ebola and Marburg, every year.
  • Emerging diseases can result in major economic and social costs, even with small-scale outbreaks.
    • The SARS 2003 outbreak led to an estimated $30 billion in economic losses (over $3 million per case) from reduced commerce, travel and trade.
    • The 2014-2015 West Africa Ebola epidemic led to an estimated $53 billion in economic losses. A single Ebola patient in New York cost the city’s $4.3 million in response measures.
    • Measles outbreaks in the U.S., often initiated through importation from other countries, can lead to significant costs; a recent study from Washington state found that a 71-case measles outbreak led to societal costs of $3.4 million, or almost $50,000 per case.
  • Pandemics have even more massive economic costs, as experienced with COVID-19, which cost the U.S. alone an estimated at $16 trillion – a number four times the lost economic output from the 2008 financial crisis.
  • News broke in mid-May of the ongoing Ebola outbreak in the Democratic Republic of the Congo, and given all of the changes made by the U.S. to its foreign assistance and global health response, U.S. support is taking shape under very different circumstances and through different organizational mechanisms than in the past, but a recent KFF analysis found that the speed of the U.S. government’s response to the current outbreak is on par with the prior two outbreaks, and initial U.S. funding amounts are already surpassing the prior two outbreaks.

What to Watch

  • Implementation of the America First Global Health Strategy multi-year agreements with countries
  • Status of U.S. funding appropriated by Congress for bilateral GHS efforts and contributions to CEPI and the Pandemic Fund
  • U.S. international engagement in pandemic preparedness and response

The Trump Administration’s Foreign Aid Review: Status of U.S. Support for Gavi, the Vaccine Alliance

Published: Aug 6, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on the U.S. and Gavi

  • Gavi, the Vaccine Alliance (Gavi), is an independent public-private, multilateral financing entity created in 2000. It raises and pools resources from multiple donors and in turn, disburses approximately $1.7 billion per year to support procurement and distribution of vaccines in low- and middle-income countries (LMICs).
  • Gavi supports vaccines against 20 infectious diseases, and hosts the global emergency vaccine stockpiles against Ebola, yellow fever, meningitis, and cholera. By playing a market shaping role through pooled procurement, demand forecasting, support for regional manufacturing capacity, and other strategies, Gavi helps to drive down prices for vaccines in LMICs.
  • Gavi reports that it has helped to immunize more than 1.2 billion children in 78 LMICs, preventing more than 20 million deaths, and generating economic benefits estimated at more than $280 billion, since 2000.
  • The U.S. government was one of the original donors to Gavi and had been its third largest contributor in recent years, providing 13% of its funding since its inception. Gavi also had a donor liquidity partnership with the U.S. International Development Finance Corporation (DFC) allowing Gavi to quickly access up to $1 billion from a “Rapid Financing Facility” to support routine immunization and pandemic response, backed by forthcoming donor pledges. Additionally, the U.S. was the largest donor to COVAX, the international effort housed at Gavi that supported the development, procurement, and delivery of COVID-19 vaccines to LMICs (COVAX ended in 2023).
  • Only LMICs whose most recent Gross National Income (GNI) per capita is below a certain threshold are eligible for Gavi assistance (56 countries in 2026). Countries are required to co-finance a portion of their vaccines on a sliding scale. To date, 19 countries have graduated from Gavi assistance.
  • Gavi had been the primary mechanism by which the U.S. government supported the procurement of vaccines for LMICs. The USAID bilateral maternal and child health program had complemented Gavi by supporting in-country capacity building and immunization campaigns and, prior to its dissolution in 2025, USAID had managed the U.S. partnership with Gavi.
  • Every five years, Gavi replenishes funding through “pledging conferences”. For the 2026-2030 period, Gavi secured more than $9 billion towards a target budget of $11.9 billion, which it estimates would save at least 8 million lives by 2030.
  • Prior to the start of the Trump administration, U.S. funding provided to Gavi in FY 2024 was $300 million.

Current Status of U.S. Support for Gavi:

  • Stop-work order: The foreign aid review’s stop-work order initially froze all U.S. bilateral programming but was not applied to Gavi or other multilateral institutions. The administration subsequently announced that it canceled 86% of all USAID awards. KFF analysis finds that of 770 global health awards identified, 80% are listed as terminated, including the main Gavi contract as well as the COVAX contract. Gavi reports that it has not received a termination notice for its main contract, although it did receive one for COVAX (all U.S. funding was already disbursed to COVAX in 2021).
  • International organizations review: A second executive order, calling for a 180-day review of U.S. participation in all international intergovernmental organizations, was initiated. Per the order, the purpose of the review was to determine which are “contrary to the interests of the United States and whether such organizations, conventions, or treaties can be reformed”. Gavi was not on the list of 66 international organizations from which the U.S. withdrew, per a January 7, 2026, presidential memorandum.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and that any remaining USAID operations would be absorbed by the State Department, including global health activities which would be integrated into its Bureau of Global Health Security and Diplomacy (GHSD). Delivery of lifesaving vaccines is listed among the USAID activities to be continued at GHSD, although currently the relationship with Gavi is being managed through the Office of Global Affairs at the Department of Health and Human Services. On May 29, 2025, the State Department further notified Congress of its proposed reorganization plan, and with the dissolution of USAID, programs moved in July 2025.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. While the strategy and country agreements include the importance of polio and malaria vaccination and metrics for measuring their delivery, Gavi is not mentioned, and the U.S. has not announced how it will procure these vaccines.
  • Funding: The Trump administration has not included funding for Gavi in its budget requests, including its FY27 budget request that stated that any future funding for Gavi is “contingent on the organization making necessary reforms and meeting certain benchmarks on vaccine safety.” While Congress appropriated $300 million for U.S. contributions to Gavi in FY 2025 and FY 2026, the current administration has not provided funding to Gavi after citing concerns about vaccine safety, despite Gavi following globally-recognized scientific standards and evidence. Gavi has committed to working toward accelerating its transition to different vaccines, in partnership with its Board and countries, and based on manufacturers ability to expand production capacity, among other factors. On July 29, 2026, the administration announced it would “immediately release” $600 million in Congressionally-appropriated FY25 and FY26 funding to Gavi.
  • U.S. representation on the Gavi Board: The U.S. historically played a role in Gavi’s governance, including as a Board and committee member, but with the suspension of U.S. funding by the Trump administration, the U.S. is no longer eligible to be part of the Board. In its recent announcement that it would resume funding, the administration stated that the U.S. “expects to resume its place on the Gavi Board.”   
  • Potential impact on health outcomes: The loss of U.S. support for Gavi would affect procurement of vaccines for LMICs, with particular impact on children. Gavi estimates that loss of funding could result in 75 million children not receiving routine vaccinations over the next five years, leading to more than 1.2 million children dying as a result. Reductions in vaccine stockpiles could also impact outbreak control.

What to Watch

  • Implementation of the America First Global Health Strategy
  • Status of U.S. funding appropriated by Congress for Gavi and the U.S. role in Gavi governance
  • Further results of the administration’s international organizations review
  • Impact of U.S. changes to global health programs on health outcomes

How Much and Why Premiums Are Going Up for Small Businesses in 2027

Published: Aug 6, 2026

Small businesses that offer health insurance to their employees could see health costs rise in 2027, according to an analysis of preliminary rate filings from all 50 states and DC. Nearly 300 insurers offering small group coverage reported a median proposed premium increase of 14% for next year.

Small group insurers say rising medical prices, including for hospitalizations, physician care, and prescription drugs, and increased utilization are major drivers of the premium increases. Among the other drivers, insurers point to the continued decline in small group plan enrollment, as more small businesses shift to alternative coverage options like self-insurance or stop offering health coverage altogether to lower costs.

The full analysis and other data on health costs are available on the Peterson-KFF Health System Tracker, an online information hub dedicated to monitoring and assessing the performance of the U.S. health system.

The Facts About Medicare Spending

Published:

Table of Contents

Introduction

Copy link to Introduction

Medicare, the federal health insurance program for people ages 65 and over and younger people with long-term disabilities, plays a major role in the U.S. health care system.

Medicare provides health insurance coverage for 70 million people, 20% of the U.S. population – a share which will grow larger in the coming decades. Medicare spending comprised 14% of the federal budget in 2025 and 21% of national health care spending in 2024. Given Medicare’s essential role as a source of coverage for an aging population and the importance of sustaining the program for future generations, Medicare is often part of discussions about total federal government spending, health care spending in the U.S., and the affordability of health care costs.

This brief provides key data about Medicare spending to help frame these discussions.

Population Aging and Medicare Enrollment Growth

Copy link to Population Aging and Medicare Enrollment Growth

An aging population leads to higher enrollment in Medicare. With the aging of the U.S. population, the number of people covered by Medicare has increased over time and will increase further in the coming decades. At the same time, the Medicare population will include a growing number of people ages 80 and older.

Figure 1

Medicare Spending Trends

Copy link to Medicare Spending Trends

Growth in total Medicare spending has been driven in part by an increase in the number of people enrolled in Medicare. Higher total Medicare spending has also been driven by growth in health care spending per Medicare beneficiary, which is influenced by increasing volume and use of services, new technologies, and rising prices. Rising spending on Medicare Advantage has also contributed to growth in total Medicare spending (discussed more below). Looking to the future, these factors will continue to play a role in Medicare spending growth.

Figure 2

Growth in Medicare spending per person over time has historically been on par with or lower than spending per person with private insurance, but may increase in the coming decade. Between 2010 and 2025, growth in spending per person was lower in Medicare than in private health insurance (3.1% vs. 4.3%). In contrast to private insurers, Medicare typically sets payment rates in advance for covered services, including hospitals, physicians, and other services (except prescription drugs). As a result, Medicare payments for these services are generally lower than rates paid by private insurers. For example, private payment rates for all hospital services are about double Medicare rates, on average.

Between 2025 and 2034, growth in spending per person is projected to be higher in Medicare than in private health insurance (6.0% vs. 4.9%), reflecting the aging of the population during this period, among other factors.

Figure 3

Spending on Medicare Benefits and Medicare Advantage

Copy link to Spending on Medicare Benefits and Medicare Advantage

Spending on physician services and on Medicare Advantage accounts for a growing share of Medicare spending. Medicare now spends more on physician and outpatient services covered under Medicare Part B, including drugs administered by physicians, than hospital services covered under Medicare Part A, or retail prescription drugs covered under Part D. This gap is expected to grow. Spending on Medicare Advantage, the private plan alternative to traditional Medicare, has also grown in recent years and is projected to continue to increase.

Figure 4

This increase in spending on Medicare Advantage in part reflects a rise in Medicare Advantage enrollment over these years. Between 2010 and 2025, the share of Medicare beneficiaries enrolled in Medicare Advantage plans more than doubled, from 25% to 54%.

Additionally, Medicare pays more to private Medicare Advantage plans for enrollees than their costs would be in traditional Medicare due to factors such as higher coding intensity and favorable selection into Medicare Advantage. These higher payments have contributed to growth in spending on Medicare Advantage and overall Medicare spending.

In 2026, payments to Medicare Advantage plans are estimated to be 114% of what traditional Medicare would have spent on the same beneficiary, on average. This amount had been decreasing after Congress made changes to how Medicare Advantage plans are paid in 2010—but it has been trending higher since 2017.

Medicare pays firms offering Medicare Advantage plans a set monthly amount per enrollee. The payment is determined through an annual process in which plans submit “bids” for how much they estimate it will cost to provide benefits covered under Medicare Parts A and B for an average beneficiary. Medicare also adjusts payment to Medicare Advantage plans based on certain factors, such as the health status of enrollees. Read KFF’s explainer to understand the details of how Medicare pays private plans.

Medicare Part A Solvency Challenges

Copy link to Medicare Part A Solvency Challenges

The Medicare Hospital Insurance (Part A) Trust Fund faces solvency challenges in the near future. Higher Medicare Part A spending, driven by enrollment growth and an increase in spending per beneficiary, coupled with a shortfall in revenues needed to pay for all Part A covered benefits, is projected to deplete the reserves in the Part A Trust Fund within 7 years.

Figure 5

Growth in Out-of-Pocket Spending

Copy link to Growth in Out-of-Pocket Spending

Increases in Medicare spending have led to higher Medicare premiums and deductibles for beneficiaries. Taken together the cost of Medicare Part A and B premiums and cost sharing represents roughly 18% of the average Social Security benefit in 2026, up from 14% in 2000. (Most beneficiaries do not pay a Part A premium. However, beneficiaries ages 65 and older who have paid fewer than 10 years of Medicare payroll taxes and some younger beneficiaries with disabilities are required to pay a premium for Part A coverage.) While most beneficiaries have other sources of income in addition to Social Security to help cover these expenses, there are also other out-of-pocket health care costs that beneficiaries could incur, such as premiums for prescription drug coverage and cost sharing for medications and physician visits, as well as costs for services not covered by Medicare, such as dental care and long-term services and supports.

Figure 6

Conclusion

Copy link to Conclusion

Medicare faces spending pressures due to rising enrollment and rising health care costs. Consideration of possible changes to Medicare to sustain the program for the long run—such as changes in payments to providers and Medicare Advantage plans, changes in benefits, or additional revenues—will involve careful deliberation about the effects on federal spending, total health care spending, health care providers, and access to quality care and the affordability of health care for Medicare’s growing number of beneficiaries.

Data Sources

Copy link to Data Sources

This resource, originally published on April 26, 2022, was most recently updated with new data in July 2026.

The Boards of Trustees of the Federal Hospital Insurance and Federal Supplementary Medical Insurance Trust Funds, 2026 Annual Report of the Boards of Trustees of the Federal Hospital Insurance and Federal Supplementary Medical Insurance Trust Funds, June 2026.

Centers for Medicare & Medicaid Services, Chronic Conditions Data Warehouse.

Centers for Medicare & Medicaid Services, Office of the Actuary, National Health Statistics Group, National Health Expenditure Data, Table 21 Expenditures, Enrollment and Per Enrollee Estimates of Health Insurance, United States, Calendar Years 1987-2024.

Congressional Budget Office, Analysis of the President’s Budgetary Proposals for Fiscal Year 2001, April 2000.

Congressional Budget Office, Baseline Projections for Medicare, various years.

Congressional Budget Office, The Budget and Economic Outlook: 2026 to 2036, February 2026.

KFF, How Medicare Pays Medicare Advantage Plans: Issues and Policy Options, November 2025.

KFF, Medicare 101: How Does Medicare Pay Hospitals, Physicians, and Other Providers in Traditional Medicare? October, 2025.

Medicare Payment Advisory Commission, March 2026 Report to the Congress: Medicare Payment Policy, March 2026.

Social Security Administration, Office of Retirement and Disability Policy, Annual Statistical Supplement, 2025, March 2026.

Social Security Administration, Office of Retirement and Disability Policy, Monthly Statistical Snapshot, January 2026, February 2025.

U.S. Census Bureau, Population Division, Projected Population by Five-Year Age Group and Sex for the United States, Main Series: 2022-2100.

U.S. Census Bureau, Laura Blakeslee, Zoe Caplan, Julie A. Meyer, Megan A. Rabe, and Andrew W. Roberts, Age and Sex Composition: 2020, C2020BR-06, May 2023.

How Much and Why ACA Marketplace Premiums Are Going Up in 2027

Authors: Matt McGough, Jared Ortaliza, Ashley Ferguson, Imani Telesford, Shameek Rakshit, Lynne Cotter, and Cynthia Cox
Published: Aug 3, 2026

Note: This brief was originally published on July 8 and updated on August 3, 2026 to include proposed 2027 rates from all 50 states and the District of Columbia.

ACA Marketplaces insurers are proposing a median premium increase of 15% in 2027, according to KFF’s updated analysis of 276 insurers with publicly available filings across all 50 states and the District of Columbia. This is the second consecutive year of double-digit premium hikes. Last year’s median nationwide proposed rate change was 18%, and the median finalized rate change was 20%. While this proposed rate change is lower than last year, it represents the second-highest requested rate change since 2018, as premium growth had been relatively flat in this market for several years.

Based on detailed filings from 16 states and DC, rising healthcare prices—as in prior years—remain the primary driver of 2027 premium increases. Insurers cite higher costs for health services, general economic inflation, and labor shortages. They also point to factors unique to the individual market: the expiration of enhanced premium tax credits at the end of 2025 and a related increase in the risk pool’s morbidity, as contributing to rising rates for 2027.

The full analysis and other data on health costs are available on the Peterson-KFF Health System Tracker, an online information hub dedicated to monitoring and assessing the performance of the U.S. health system.

Five Key Facts About People Experiencing Homelessness

Published: Jul 31, 2026

Editorial Note

This brief, originally published on September 9, 2025, was updated with the most recently available data on July 31, 2026.

According to the most recent data available from the U.S. Department of Housing and Urban Development (HUD), nearly 746,000 people were experiencing homelessness on a single night in January 2025, an over 30% increase from 2019, but also a 3% decrease from the highest levels ever recorded in 2024. The links between homelessness and health are complex, and past KFF research found that people with prior experiences of homelessness have disproportionate physical and mental health needs and face greater socioeconomic challenges compared to those who have never experienced homelessness. People experiencing homelessness who are unsheltered also experience higher rates of chronic homelessness, chronic disease, mental illness, and substance abuse than those who are sheltered.

This data note reviews trends in homelessness and characteristics of people who are homeless using data from HUD’s Point-in-Time (PIT) count of sheltered and unsheltered people experiencing homelessness. The PIT count is generally conducted on a single night during the last ten days of January. While the PIT count is the primary nationally standardized measure to track trends in homelessness over time, these estimates likely undercount the total number of people experiencing homelessness, particularly among the unsheltered, due to challenges locating individuals who are unsheltered, local staffing capacity, and weather. The PIT count also does not include people who are staying with family or friends, referred to as “doubling up”, in other unstable housing situations, or living in permanent supportive housing.

These data capture a look at homelessness amid a number of federal policy changes aimed at clearing homeless encampments, limiting provisions for housing alternatives, and potentially resulting in institutionalization among people experiencing homelessness. President Trump signed an executive order in July 2025 on homelessness, mental health, and substance use that encouraged states to remove unhoused people from public spaces, following nationwide passage of Supreme Court-backed local laws making it easier for law enforcement to ticket, fine, or arrest people sleeping on public property. HUD proposed to shift homelessness services spending away from “Housing First” programs–which provide immediate housing without preconditions such as sobriety or mandatory mental health treatment—towards “transitional housing” programs, and require local homelessness services entities to cooperate with law enforcement to prohibit homeless encampments, but was blocked by court ruling in June 2026. Most recently, the Department of Justice (DOJ) issued an opinion in June 2026 and a notice in July 2026 challenging the longstanding interpretation of the Olmstead Supreme Court decision, signaling narrower federal enforcement of the integration mandate, which has helped spur state investment in rental assistance, supportive housing, and community services for people with disabilities. These changes could potentially result in fewer community services and increased institutionalization among people experiencing homelessness. 

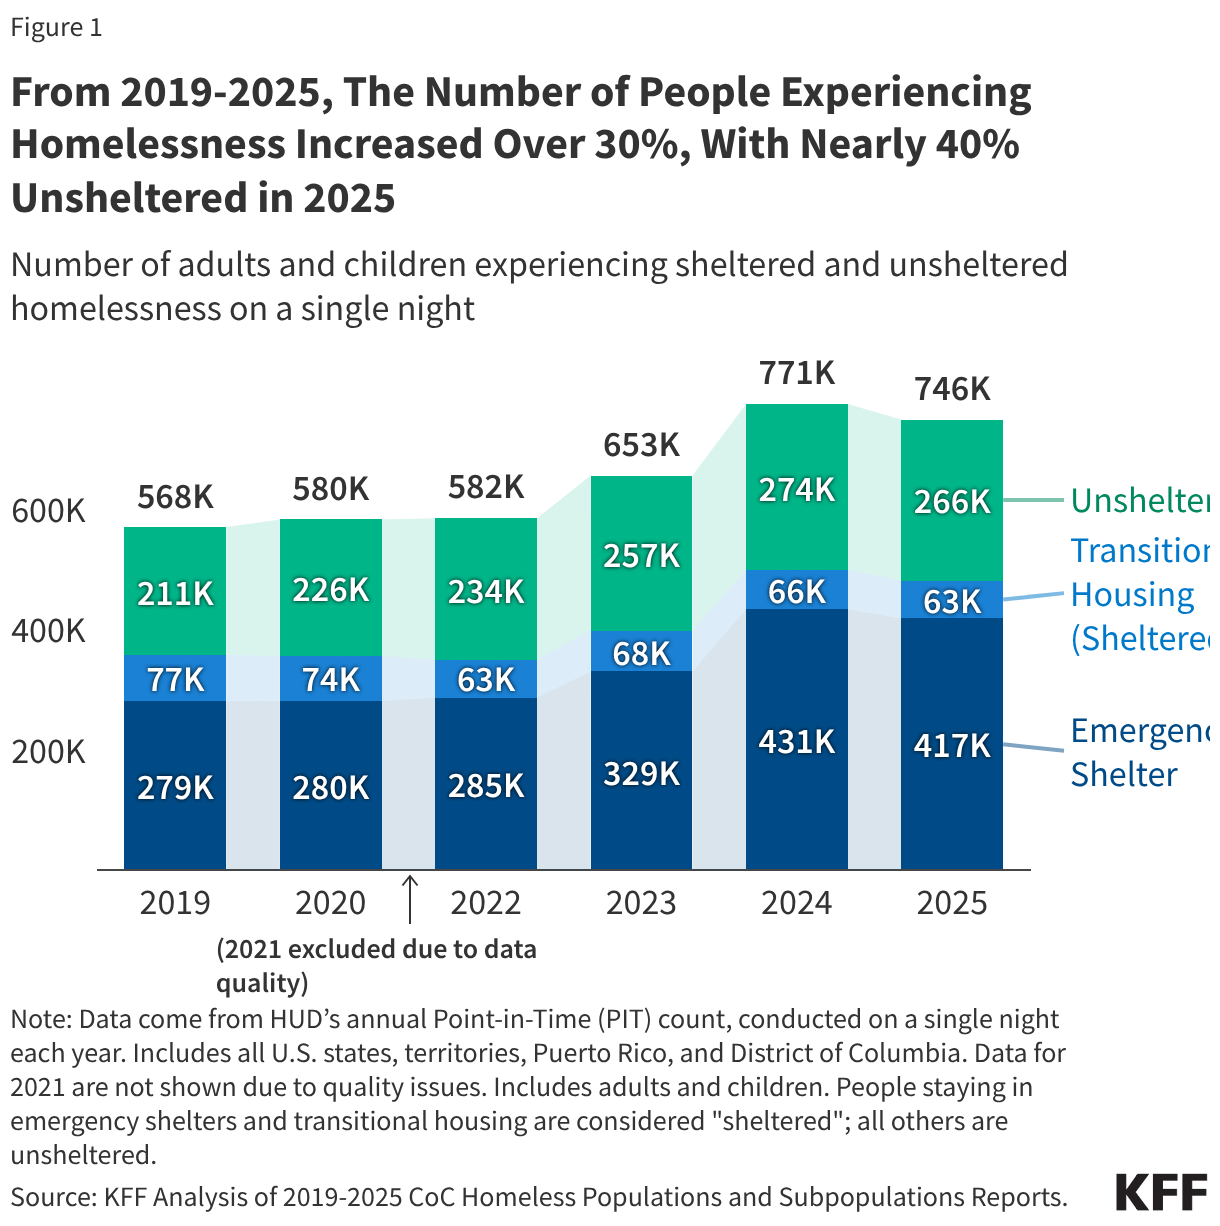
1. From 2019 to 2025, the number of people experiencing homelessness on a single night increased by over 30% to nearly 746,000 people, with nearly four in ten (36%) staying in unsheltered locations.

The HUD PIT survey counts people experiencing homelessness in both sheltered and unsheltered settings on a single night. People are counted as unsheltered if they sleep in locations not ordinarily used as a regular sleeping accommodation, such as cars, parks, abandoned buildings, or campgrounds. The remainder of people experiencing homelessness were in sheltered locations, with nearly six in ten (56%) staying in emergency shelters and nearly one in ten (8%) in transitional housing, which is temporary housing with supportive services (Figure 1).

Between 2019 and 2025, the number of people experiencing homelessness rose by 31%. This increase was primarily driven by the growth in the number of people staying in emergency shelters and experiencing unsheltered homelessness, while the number of people in transitional housing declined over the same period. According to HUD, rising housing costs and the end of the COVID-19 public health emergency in May 2023, which ended the eviction moratorium and other income and safety net programs, drove recent increases. Counts of people experiencing homelessness peaked in 2024 and then decreased 3% from 2024 to 2025, with nearly 60% of the decrease driven by a reduction in the number of people in emergency shelters.

Beyond shifts in sheltered and unsheltered homelessness, the share of people experiencing homelessness identified as “chronic homelessness”—defined by HUD as having a disability, including physical, mental, developmental, substance use-related, or HIV/AIDS-related disabilities, and experiencing long-term or repeated episodes of homelessness of at least 12 months—increased from 19% in 2019 to 23% in 2025 (from about 106,000 to 170,000). However, the share of adults experiencing homelessness who were veterans fell from 8% in 2019 to 5% in 2025 (from about 37,000 to 33,000), similar to their share of the general adult population (6%). An increase in housing assistance programs from the Department of Veterans Affairs (VA) in recent years likely drove this decrease.

From 2019-2025, The Number of People Experiencing Homelessness Increased Over 30%, With Nearly 40% Unsheltered in 2025 (Stacked column chart)

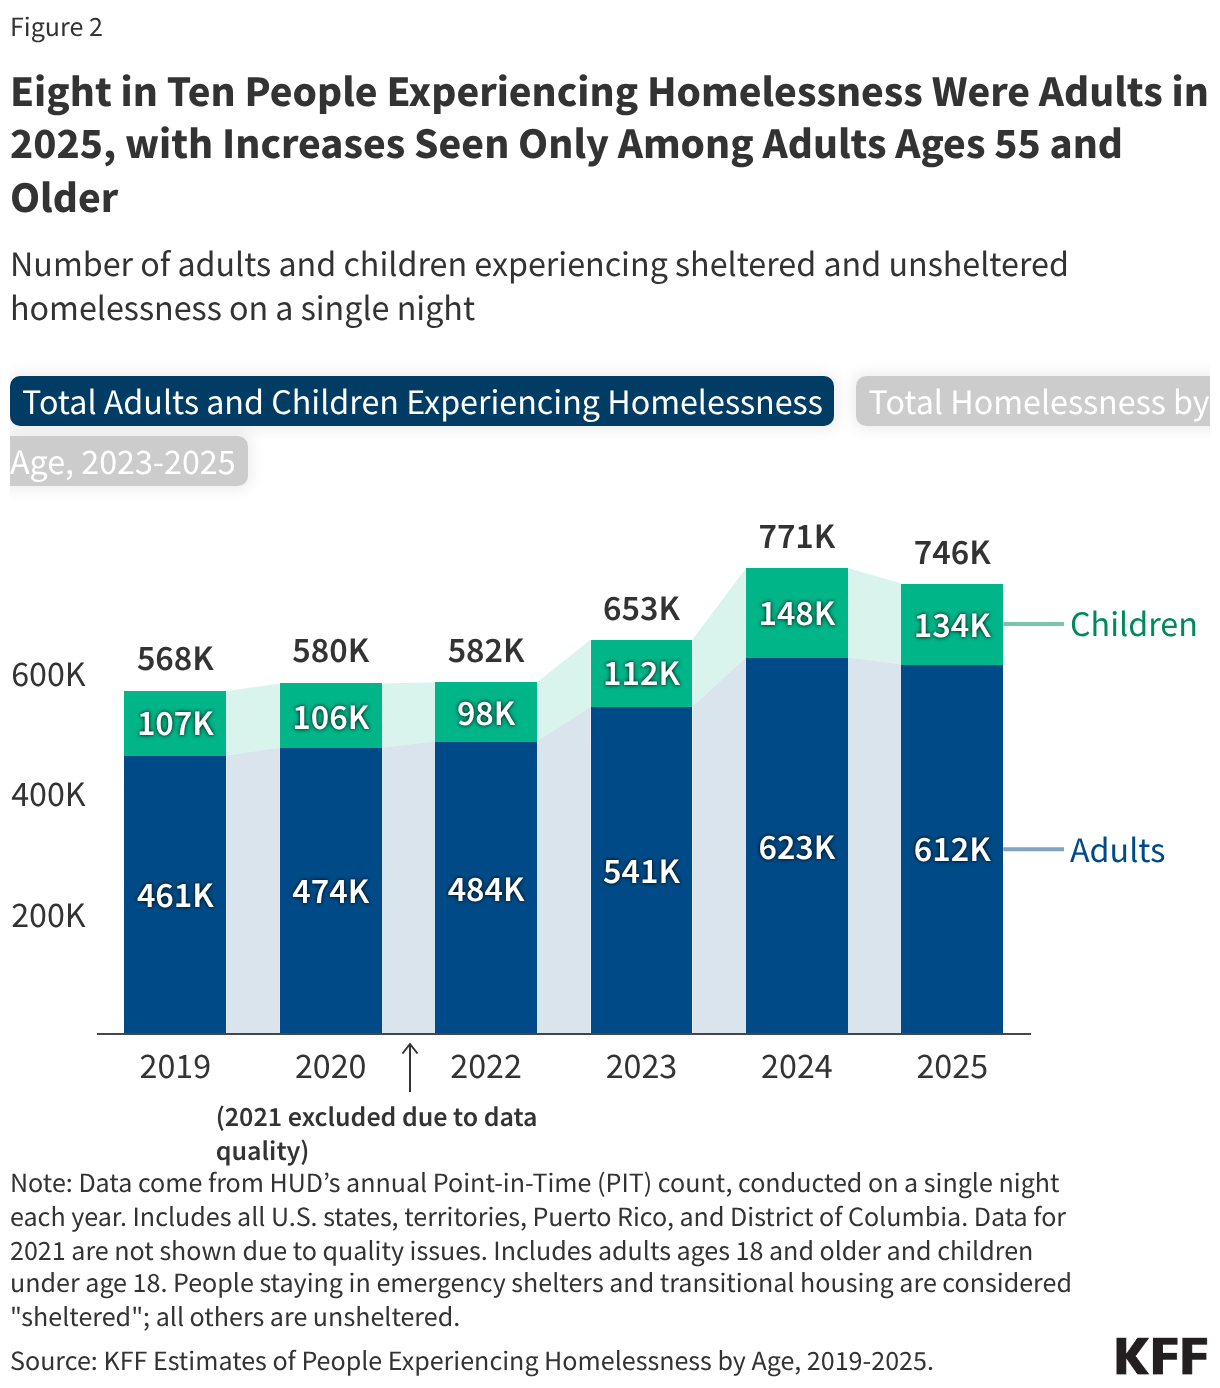
2. In 2025, over eight in ten (82%) people experiencing homelessness were adults, with decreases in the number of people experiencing homelessness seen across age groups since 2024 except among adults ages 55 and older.

On a single night in January 2025, there were about 612,000 adults and 134,000 children experiencing homelessness, with adults consistently representing about eight in ten of all people experiencing homelessness since 2019 (Figure 2). The number of children experiencing homelessness increased 25% from 2019 to 2025. However, after several years as the fastest-growing age group among people experiencing homelessness, the number of children experiencing homelessness fell 10% (from about 148,000 to 134,000) from 2024 to 2025. Most households with children experiencing homelessness are sheltered, as children made up less than one in ten (4%) unsheltered people in 2025. Housing insecurity during childhood is associated with negative health outcomes later in life, including anxiety and depression. The number of adults experiencing homelessness fell 11% among adults ages 18-24 and 2% among adults ages 25-54 from 2024 to 2025 but increased among those ages 55 and older by 2%. While long-term data for these specific age ranges are not available prior to the 2023 PIT count, research found that adults born between 1955 and 1965 have comprised a disproportionate share of single adults experiencing sheltered homelessness across several decades, suggesting that the aging of this cohort has contributed to the recent rise in adults ages 65 and older experiencing homelessness.  

Eight in Ten People Experiencing Homelessness Were Adults in 2025, with Increases Seen Only Among Adults Ages 55 and Older (Stacked column chart)

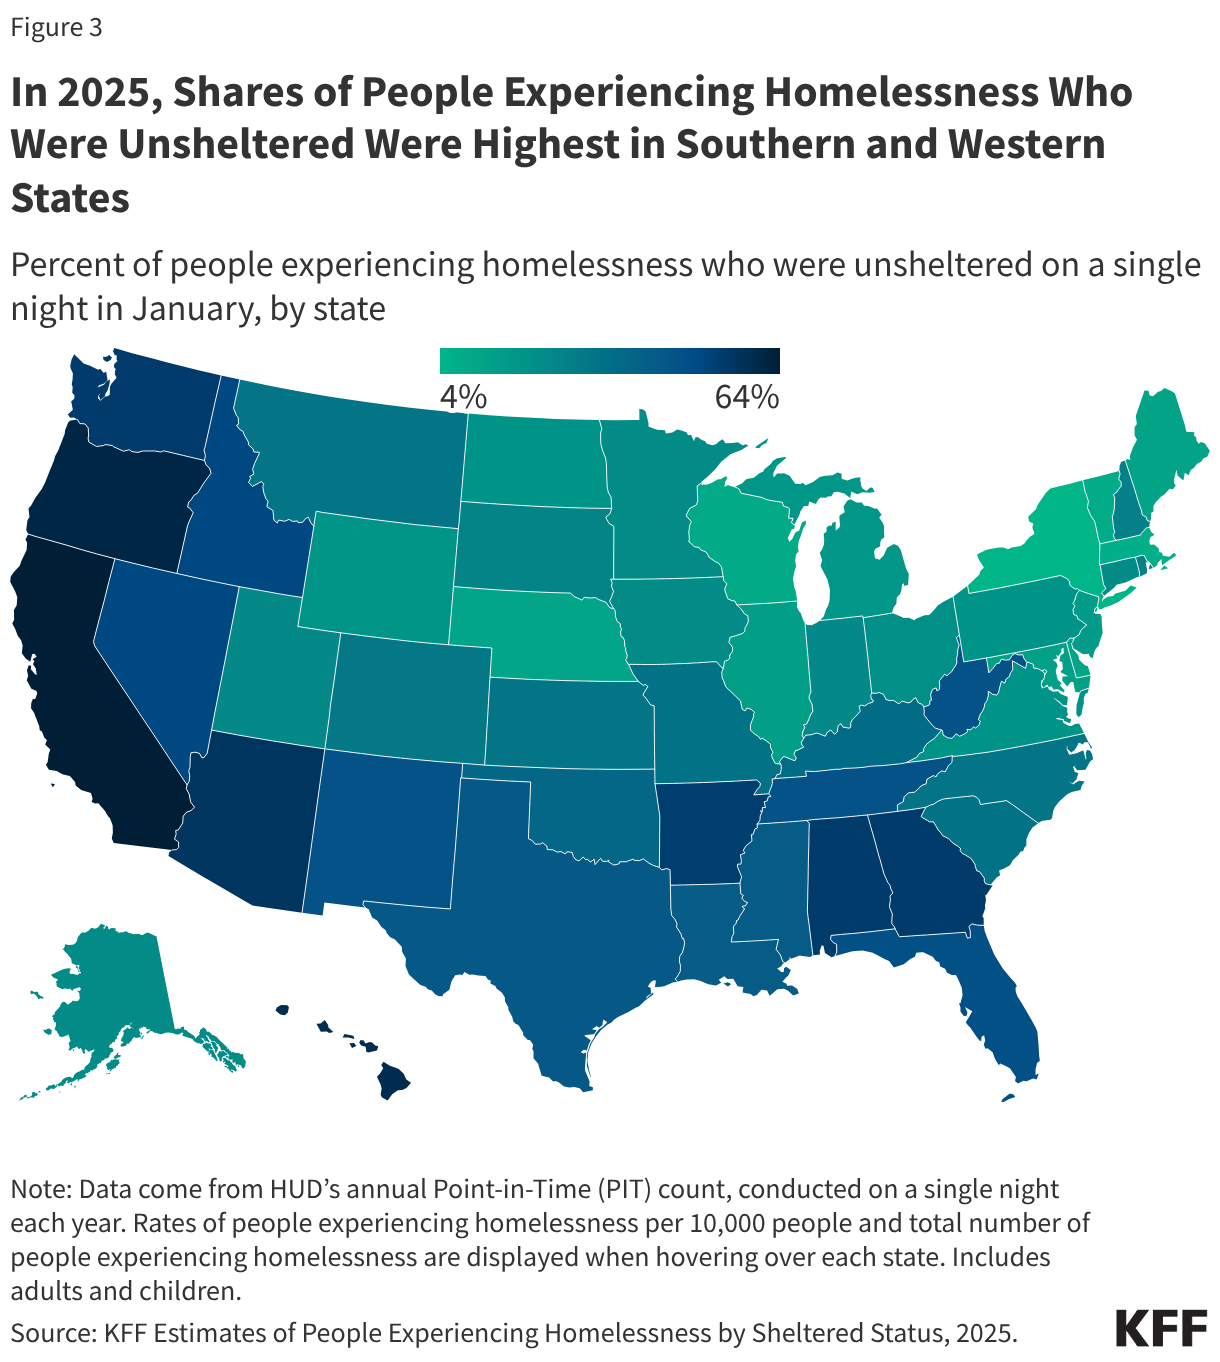
3. In 2025, Southern and Western states had higher shares of people who were experiencing homelessness who were unsheltered compared to other parts of the country.

States in the Northeast and West had higher rates of people experiencing homelessness per 10,000 people than elsewhere in the country on a single night in January 2025 (Figure 3). The share of people experiencing homelessness who were unsheltered by state were highest in Southern and Western states, including in California (64%), Oregon (61%), Arizona (56%), and Georgia (54%). In contrast, the shares of people experiencing homelessness who were unsheltered were lowest in New York (4%) and Massachusetts (6%), despite these states having relatively high rates of people experiencing homelessness per 10,000 people. These patterns may reflect a combination of local factors, including climate, housing costs, shelter capacity, right to shelter laws, and law enforcement policies that bring more people into emergency shelters or other sheltered housing.

In 2025, Shares of People Experiencing Homelessness Who Were Unsheltered Were Highest in Southern and Western States (Choropleth map)

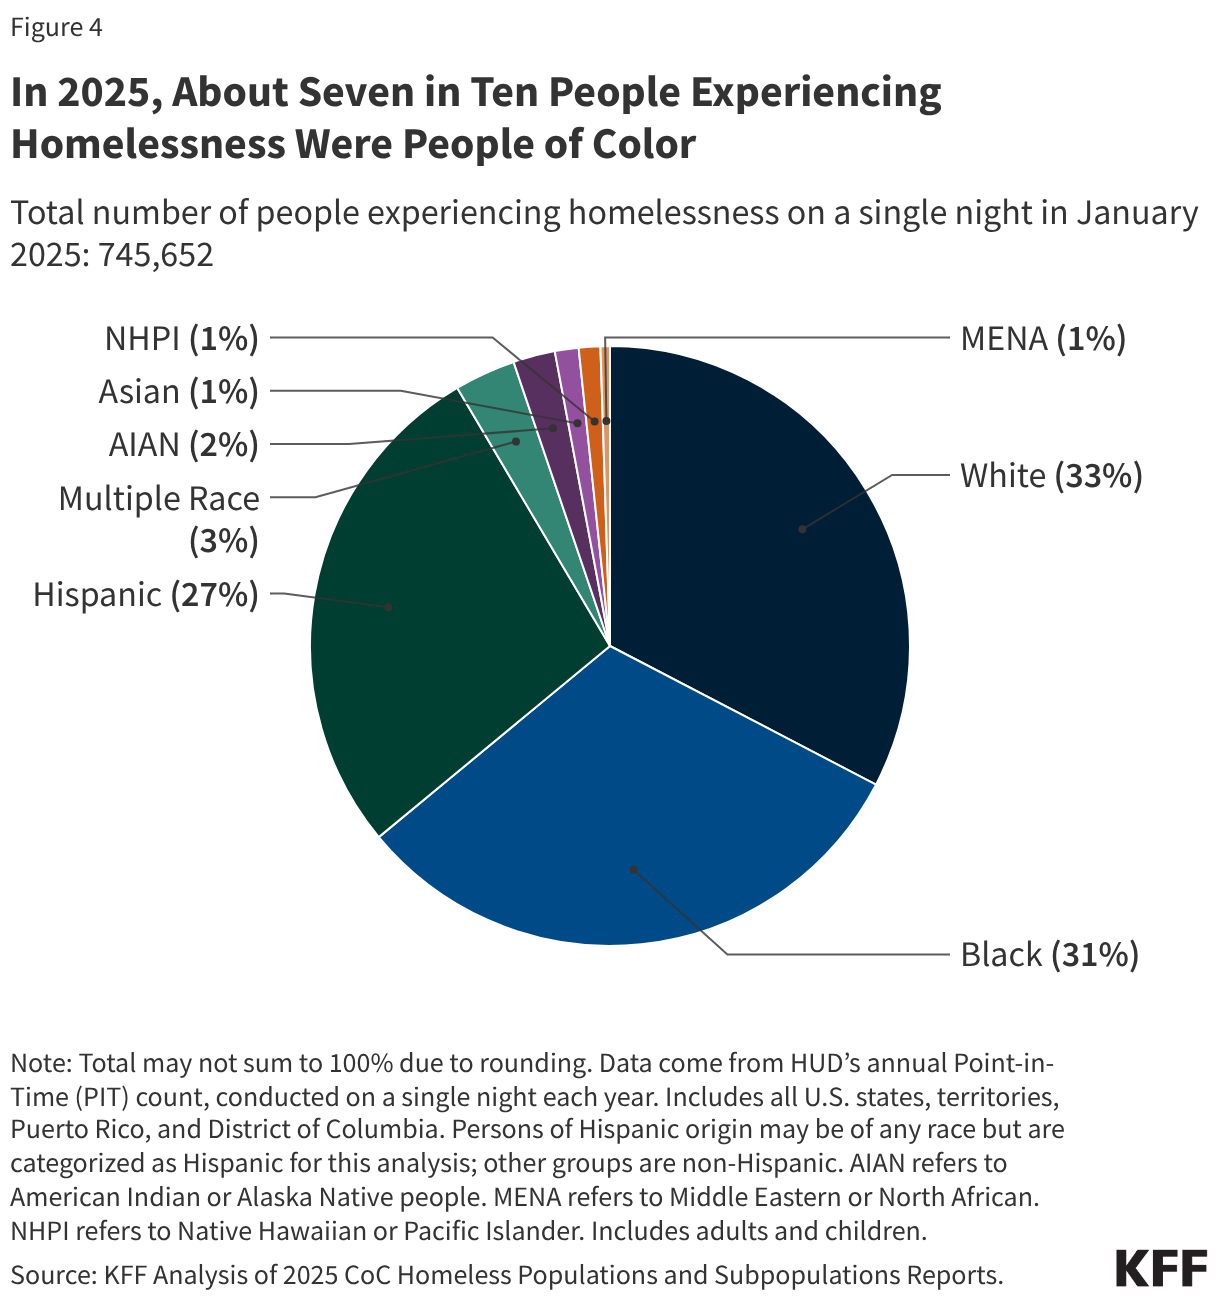
4. In 2025, about seven in ten (67%) people experiencing homelessness were people of color.

White (33%), Black (31%), and Hispanic (27%) people each accounted for about three in ten of people experiencing homelessness on a single night in January 2025, with other racial and ethnic groups making up smaller shares (less than 5%) (Figure 4). Black, Hispanic, AIAN, and NHPI people made up a disproportionate share of the people experiencing homelessness compared to their share of the total population.

In 2025, About Seven in Ten People Experiencing Homelessness Were People of Color (Pie Chart)

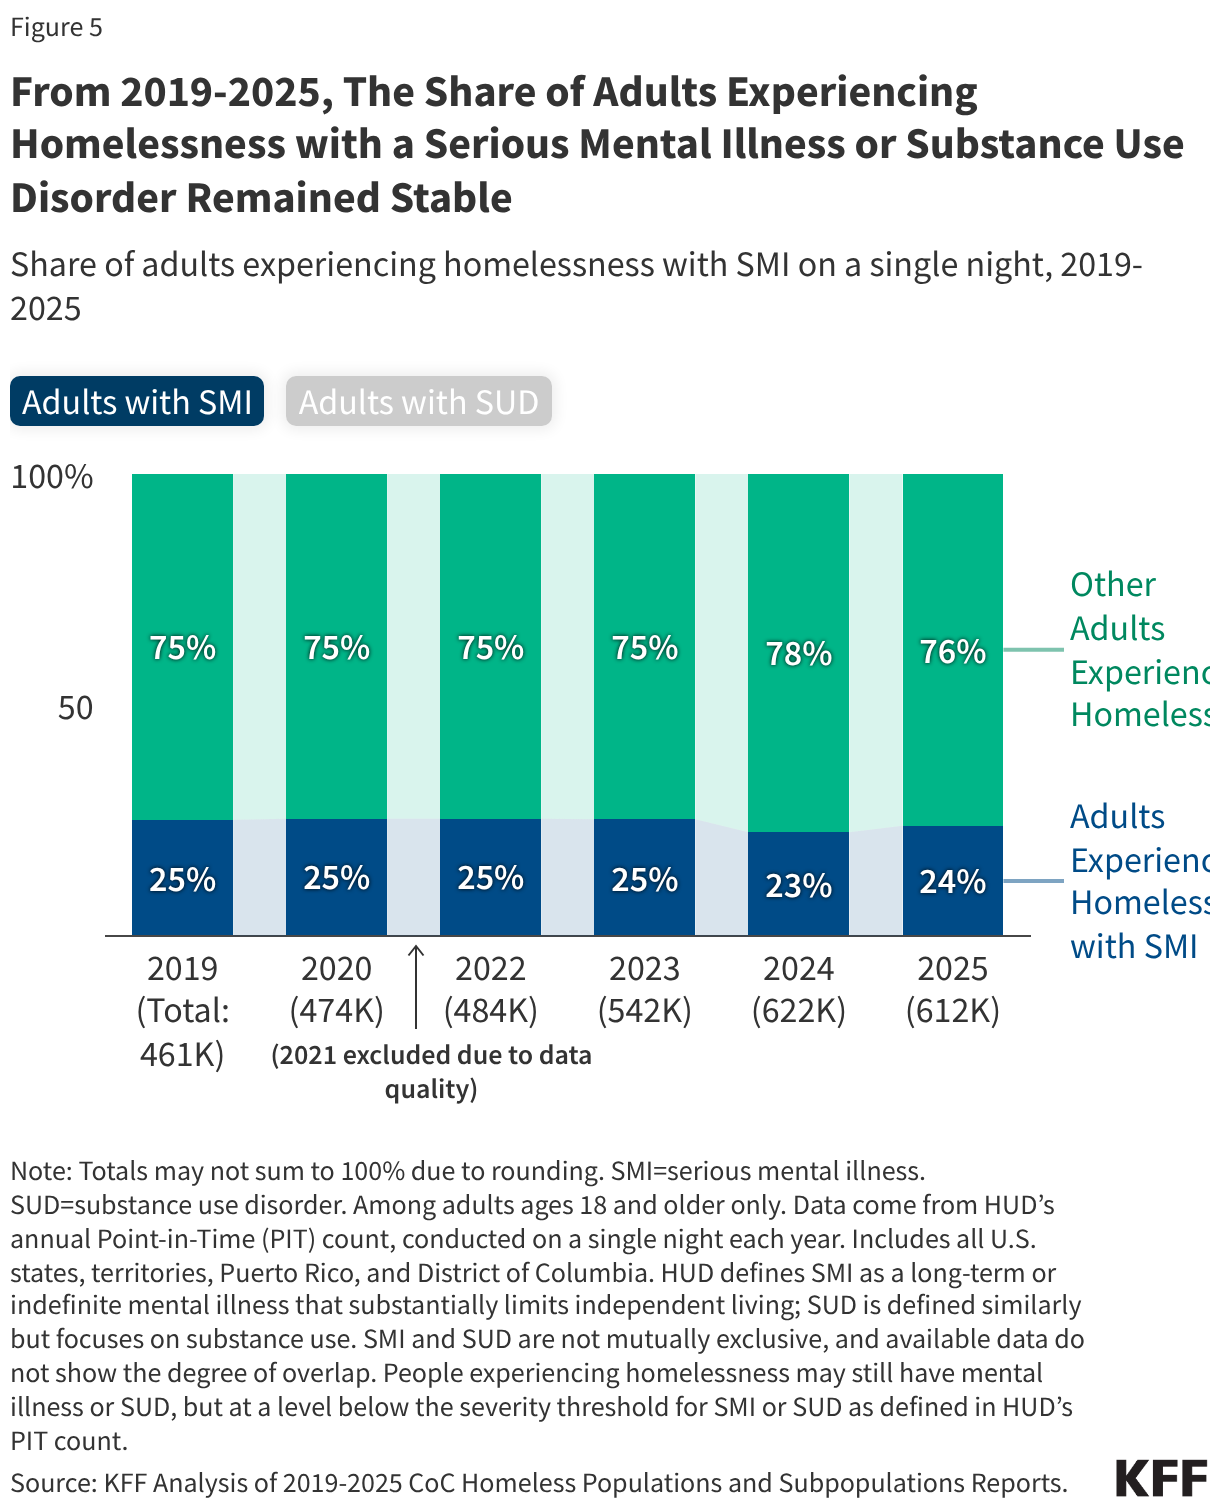
5. From 2019 to 2025, the share of adults experiencing homelessness with serious mental illness (SMI) or substance use disorder (SUD) remained stable, suggesting that rising homelessness reflects broader factors affecting both people with and without these conditions.

In 2025, about a quarter (24%, or 146,000) of adults experiencing homelessness on a single night in January met HUD’s SMI definition and nearly one in five (18%, or 112,000) had SUD according to HUD’s definition in the point-in-time count, about a 1% decrease from 2019 (Figure 5). SMI and SUD often co-occur—about one-quarter of people with SMI also have an SUD—but HUD’s publicly available data do not report the overlap of these conditions. The prevalence of SMI and SUD represents an outsized share of the population of adults experiencing homelessness as about 5-6% of adults overall have SMI according to the National Survey of Drug Use and Health (NSDUH) and 3% of adults in the general population meet NSDUH criteria for severe SUD. While homelessness among adults increased sharply from 2019 to 2025, the share of adults with SMI or SUD changed little, suggesting the increase was not concentrated among people with behavioral health conditions, and likely reflects broader pressures, such as rising housing and living costs. A Government Accountability Office (GAO) report found that a $100 increase in median rental price was linked to a 9% increase in estimated homelessness rate. Other research found increases in the number of people experiencing homelessness from 2019 to 2024 were more strongly associated with reductions in eviction moratoriums and climate-related events.

From 2019-2025, The Share of Adults Experiencing Homelessness with a Serious Mental Illness or Substance Use Disorder Remained Stable (Stacked column chart)

Health and Health Care Experiences of Uninsured Immigrants 

Published: Jul 30, 2026

Introduction

As of 2024, there were about 50 million immigrants residing in the U.S. Within this group, there were 24 million noncitizen immigrants, including lawfully present and undocumented immigrants, and 26 million naturalized citizens, who accounted for about 7% and 8% of the total population, respectively. Actions taken by the Trump administration and Congress will likely have major impacts on health and health care for immigrant families, including increasing the number of uninsured immigrants.

While undocumented immigrants have been ineligible for federally-funded health coverage programs under longstanding policy, the 2025 reconciliation law includes new eligibility restrictions for many lawfully present immigrants, including refugees and asylees, to access Medicaid and the Children’s Health Insurance Program (CHIP), subsidized Affordable Care Act (ACA) Marketplace, and Medicare coverage. The CBO estimates that 1.4 million lawfully present immigrants could lose health coverage by 2034 due to the law’s eligibility changes. Research shows that having insurance makes a difference in whether and when people access needed care. Those who are uninsured often delay or go without needed care, which can lead to worse health outcomes over the long-term that may ultimately be more complex and expensive to treat.

This brief provides data on health and health care experiences of uninsured immigrant adults based on a KFF survey of immigrant adults ages 18 and older conducted in partnership with The New York Times in Fall 2025. The data provide insight into how the projected coverage losses under the 2025 reconciliation law may impact health and health care for immigrant families as more lawfully present immigrants become uninsured. Key takeaways include the following:

Compared to those with insurance coverage, uninsured immigrant adults are more likely to not have a usual source of care and to delay or go without health care. Half of uninsured immigrant adults say that they do not have a usual source of health care other than the emergency room compared to about one in six (16%) of their insured counterparts. Further, half of uninsured immigrant adults report skipping or postponing care, twice the share of those with coverage (50% vs. 26%). Nearly one in five (18%) of all uninsured immigrant adults said their health got worse as a result of skipping or postponing health care.

Cost or lack of coverage is the primary reason uninsured immigrant adults cite for skipping or postponing care, reflecting the role insurance plays in facilitating access to care. Almost half (46%) of uninsured immigrant adults say they delayed or went without care because of cost or lack of insurance compared to 14% of insured immigrant adults. Overall, about seven in ten (69%) uninsured immigrant adults say they have had problems paying for health care (62%), housing (41%), or food (36%) in the past 12 months. In comparison, over four in ten (44%) insured immigrant adults report problems paying for health care (31%), housing (29%), or food (26%) in the past 12 months.

Consistent with other research demonstrating that parental coverage affects children’s health coverage and access to care, uninsured immigrant parents are three times as likely as those with insurance coverage (32% vs. 10%) to say they have at least one child who is uninsured. Further, over four in ten (44%) uninsured immigrant parents say any of their children delayed or skipped health care in the past 12 months compared to about a quarter (26%) of those with insurance coverage.

Findings

Characteristics of Uninsured Immigrants

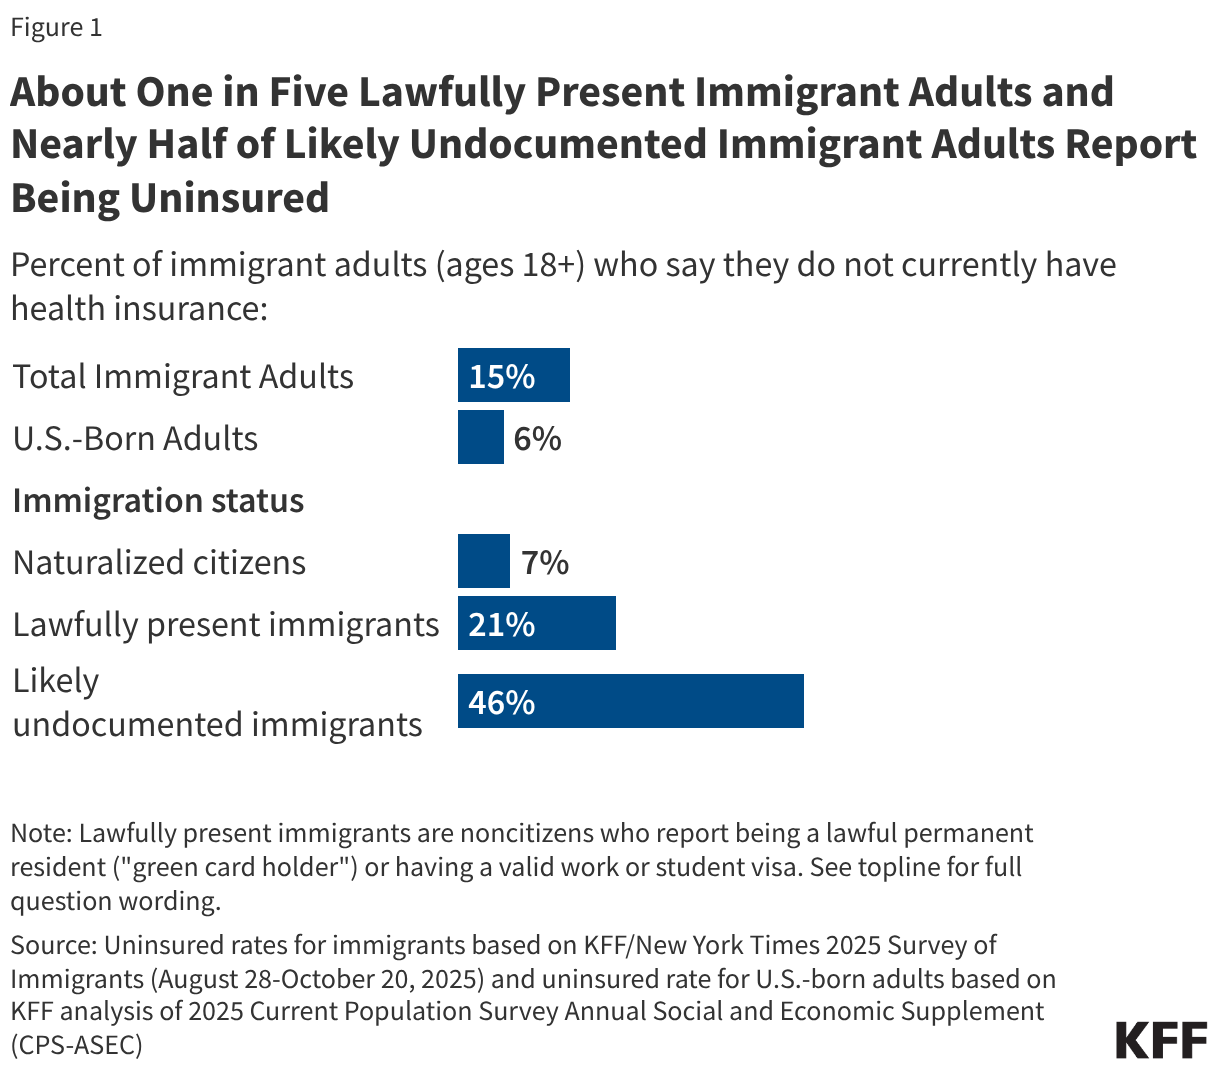
About one in seven (15%) immigrant adults age 18 and older report being uninsured as of 2025, with higher uninsured rates among those who are noncitizens, Hispanic, lower income, have limited English proficiency (LEP), or live in states with less expansive coverage. Nearly half of likely undocumented immigrant adults (46%) and one in five lawfully present immigrant adults (21%) report being uninsured compared to fewer than one in ten of their U.S.-born (6%) and naturalized citizen (7%) counterparts (Figure 1). Uninsured rates also are higher among immigrant adults who are Hispanic (27%), have lower incomes (household income of less than $40,000 per year) (23%), or have LEP (23%) compared to their White (5%), higher income (household income of $90,000 or more per year) (4%), and English proficient (10%) counterparts, likely reflecting that these groups also are more likely to be noncitizens. Further, immigrant adults who live in states that provide less expansive coverage, including not adopting the ACA Medicaid expansion to all low-income adults or any coverage expansions for immigrants, are about twice as to be uninsured compared with those living in states with more expansive policies (23% vs. 11%).

About One in Five Lawfully Present Immigrant Adults and Nearly Half of Likely Undocumented Immigrant Adults Report Being Uninsured (Bar Chart)

Access to Health Care

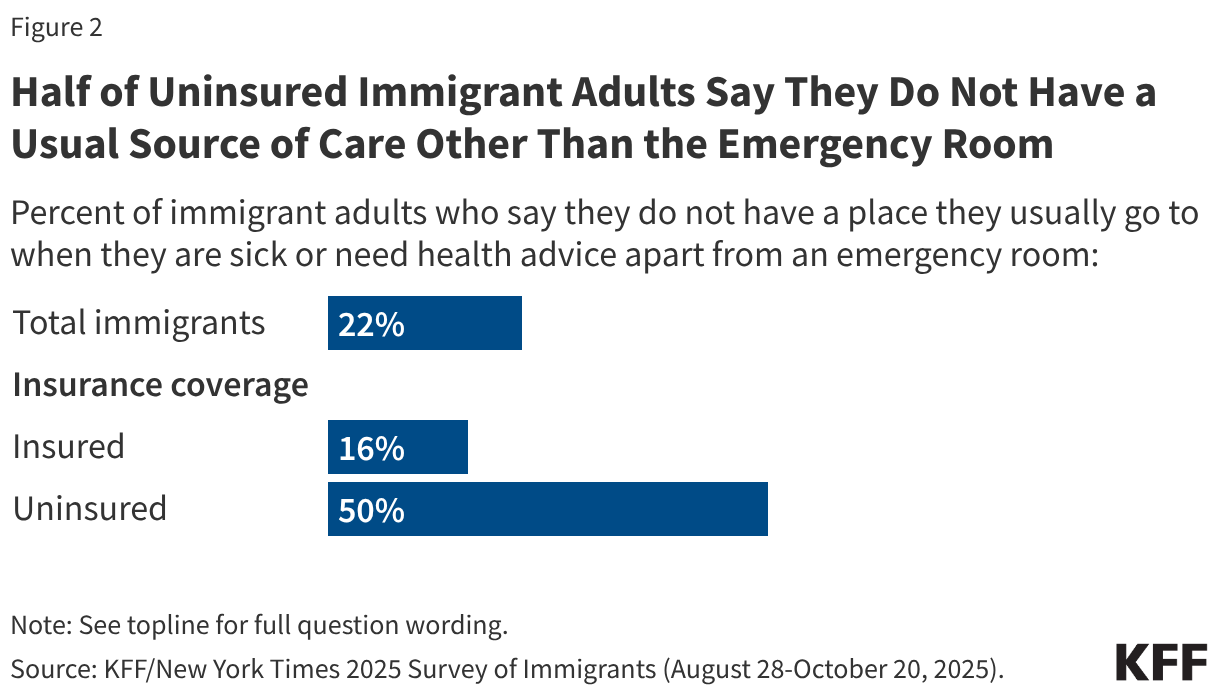
Half of uninsured immigrant adults say they do not have a usual source of care other than an emergency room (Figure 2). In comparison, about one in six (16%) insured immigrant adults say they do not have a usual source of care other than an emergency room. Research shows that having a usual source of care is associated with better access to health care even after controlling for demographic and socioeconomic characteristics.

Half of Uninsured Immigrant Adults Say They Do Not Have  a Usual Source of Care Other Than the Emergency Room (Bar Chart)

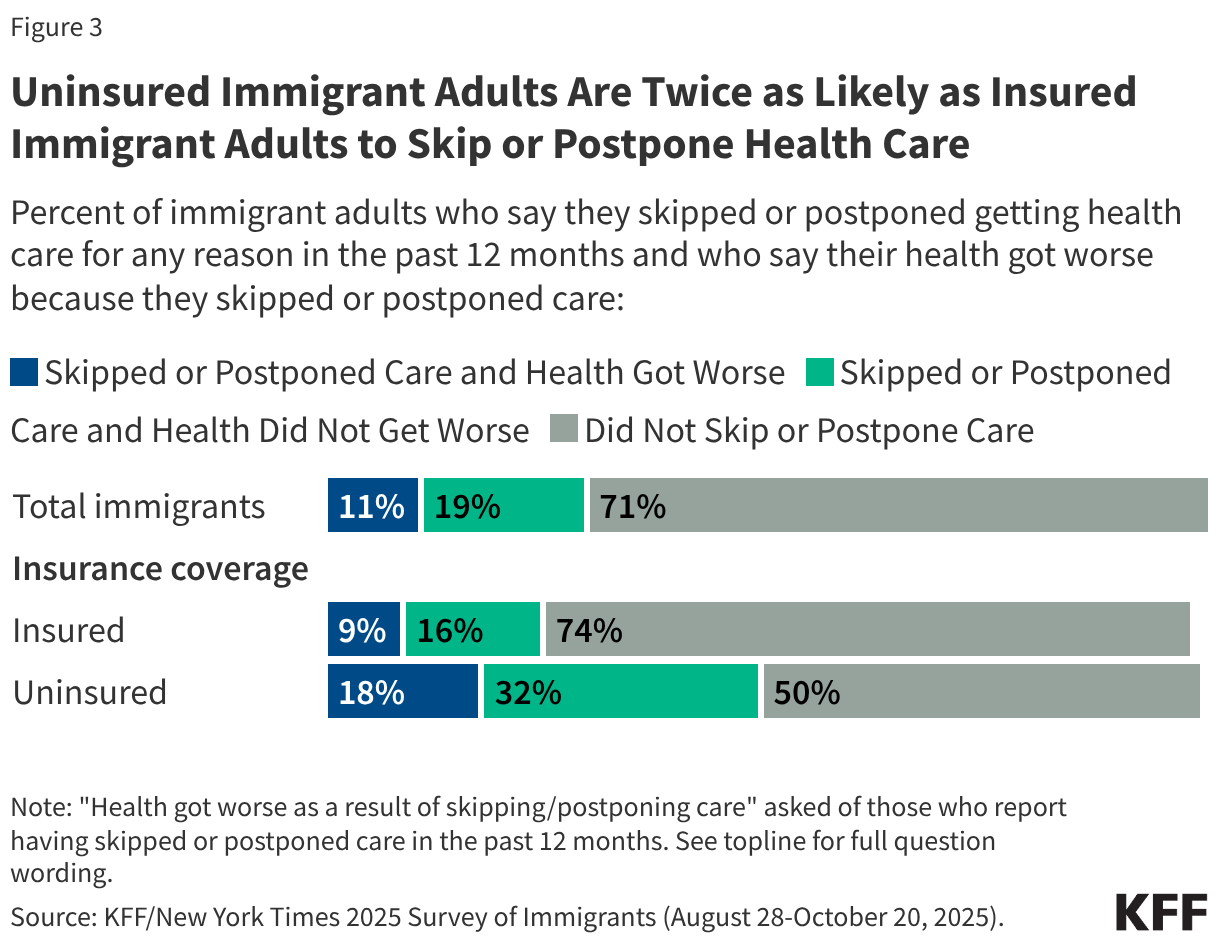
Uninsured immigrant adults are about twice as likely as those who are insured to report delaying or going without needed care (50% vs. 26%) (Figure 3). Delaying or going without needed care can contribute to health problems becoming worse and taking more time and resources to treat.  Nearly one in five (18%) of uninsured immigrant adults say they skipped or postponed health care and their health got worse compared to 9% of insured immigrant adults. 

Uninsured Immigrant Adults Are  Twice as Likely as Insured Immigrant Adults to Skip or Postpone Health Care (Stacked Bars)

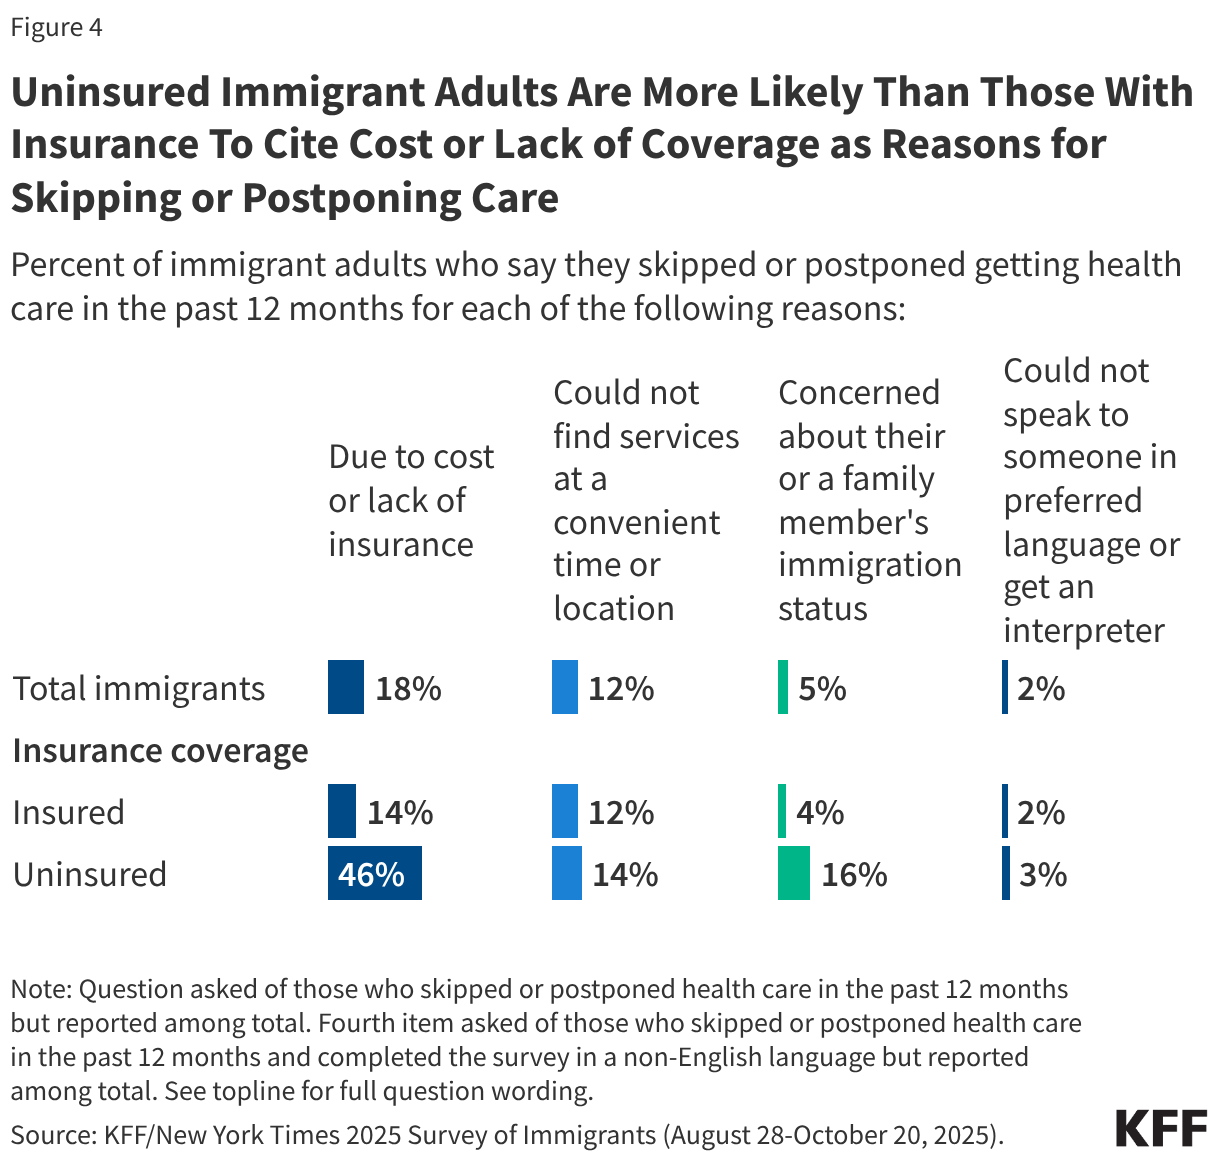
Uninsured immigrant adults are more likely than those with insurance to cite cost or lack of coverage and immigration-related concerns as reasons for delaying or going without care. Almost half (46%) of uninsured immigrant adults say they delayed or went without care because of cost or lack of insurance compared to 14% of insured immigrant adults (Figure 4). Additionally, 16% of uninsured immigrant adults identified concerns about their or a family member’s immigration status as a reason compared to 4% of insured immigrant adults, likely reflecting that uninsured immigrants include a higher share of likely undocumented immigrants. Similar shares of uninsured (14%) and insured immigrant adults (12%) cited not being able to find services at a time or location that worked for them as a reason for delaying or going without care. Language barriers were also cited by some of those with LEP.

Uninsured Immigrant Adults Are More Likely Than Those With Insurance To Cite Cost or Lack of Coverage as Reasons for Skipping or Postponing Care (Split Bars)

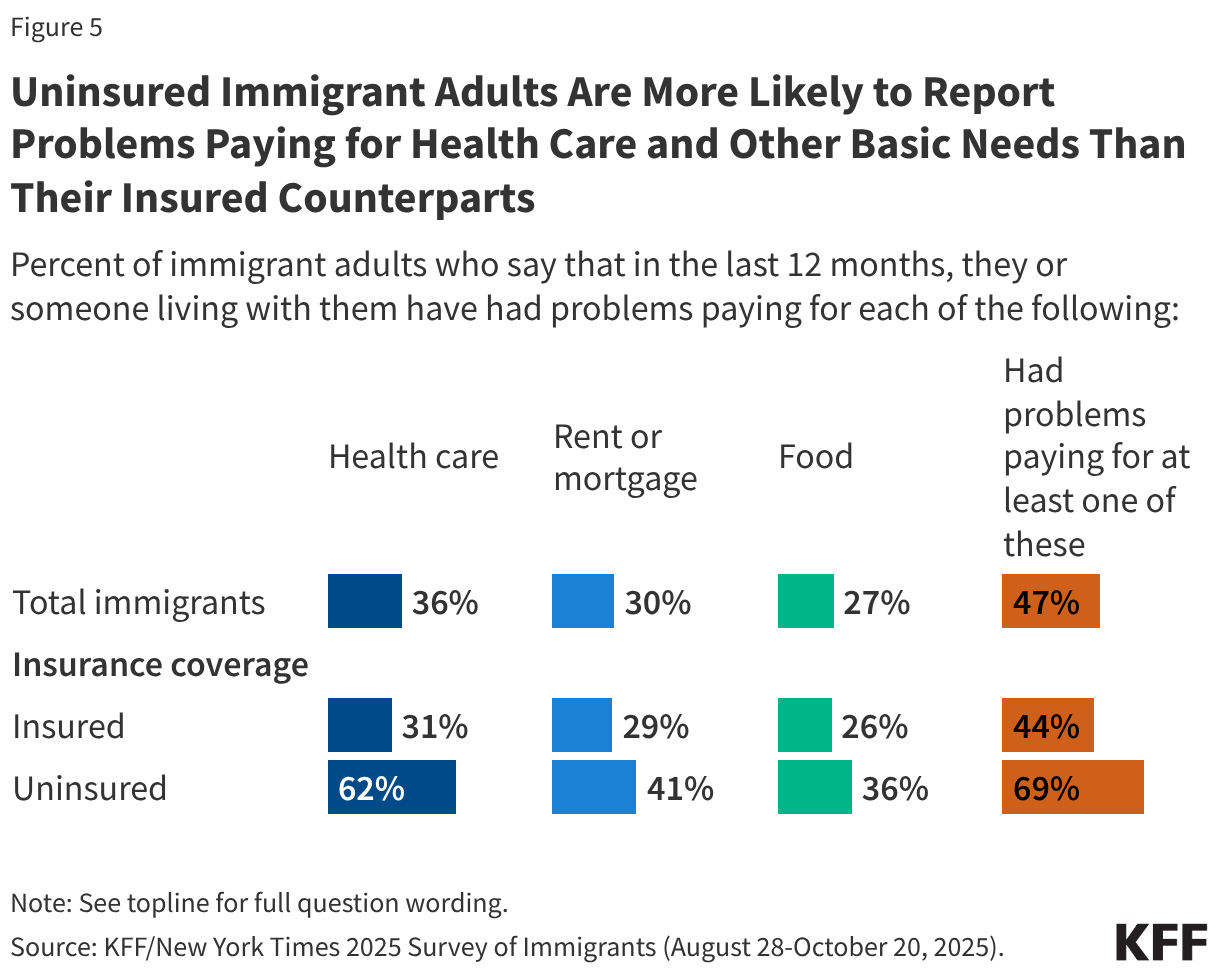
Likely reflecting their lower incomes, uninsured immigrant adults report more difficulty paying for basic needs, including health care, compared to those with insurance. Six in ten uninsured immigrant adults say that it has been harder to earn a living since January 2025 (60%) and about seven in ten (69%) say they have had problems paying for basic necessities such as health care (62%), housing (41%), or food (36%) in the past 12 months (Figure 5). These shares are higher compared to those with insurance coverage, with the largest gap in difficulty paying for health care (62% vs. 31%).

Uninsured Immigrant Adults Are More Likely to Report Problems Paying for Health Care and Other Basic Needs Than Their Insured Counterparts (Split Bars)

Impacts of Parental Coverage on Children’s Coverage and Access to Care

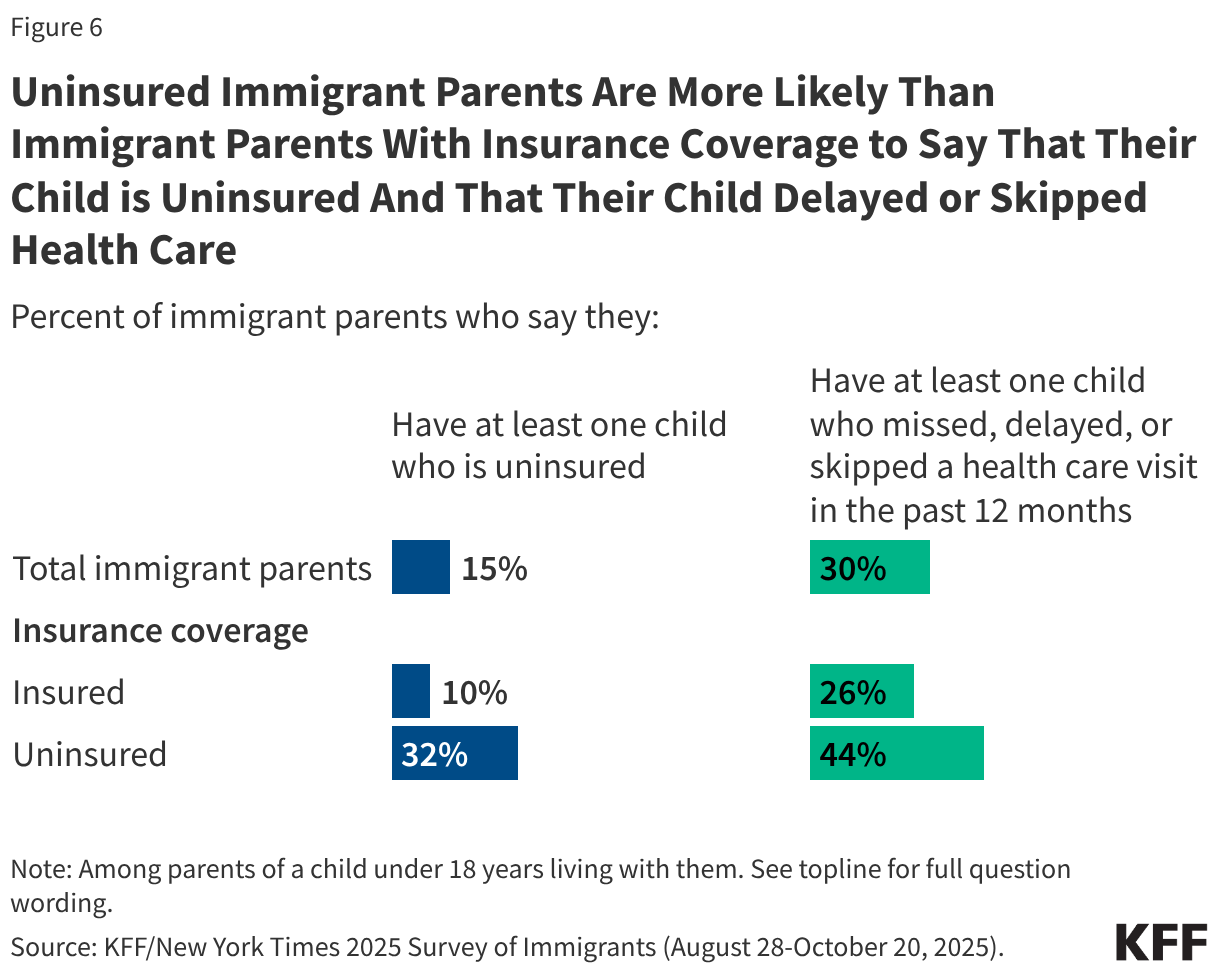
Uninsured immigrant parents are about three times as likely as insured immigrant parents (32% vs. 10%) to report at least one uninsured child as of 2025 (Figure 6). Further, over four in ten (44%) uninsured immigrant parents say any of their children delayed or skipped health care in the past 12 months compared to about a quarter (26%) of those with insurance coverage. These findings are consistent with other research showing that parental coverage impacts children’s access to health coverage and care.

Uninsured Immigrant Parents Are More Likely Than Immigrant Parents With Insurance Coverage to Say That Their Child is Uninsured And That Their Child Delayed or Skipped Health Care (Split Bars)
Poll Finding

KFF Health Tracking Poll: Mifepristone and the Midterms

Published: Jul 30, 2026

Key Takeaways

  • The latest KFF Health Tracking Poll finds that though a majority of the public has heard of the abortion medication mifepristone, public awareness of its prevalence and longstanding safety record is limited. Six in ten adults say they have heard of mifepristone, but just one in four (26%) correctly identify abortion pills as the most common way abortions are administered in the U.S. Additionally, while about four in ten (44%) adults say abortion pills are safe when taken according to a health care provider’s instruction, one in seven (15%) say they are unsafe and four in ten (41%) are unsure of their safety.
  • The FDA’s re-evaluation of the safety of mifepristone is now underway, following Health and Human Services Secretary Robert F. Kennedy Jr.’s call to the federal health agency late last year. Public confidence in the FDA to make decisions based on science when reviewing the safety of mifepristone is somewhat limited as slightly more than half (54%) say they have little to no confidence at all in this regard. Partisans differ over the motivation behind the review, with a majority of Republicans saying it was mostly to protect the health and safety of women and a similar majority of Democrats saying it was to make abortion pills more difficult to access.
  • Majorities of the public oppose laws restricting medication abortion, though Republicans lean more in support. Two-thirds of the public – including large majorities of Democrats and independents – oppose laws that would ban mifepristone nationwide (65%) and laws that would make it a crime for health care providers to mail abortion pills to patients in states with abortion bans (64%).  Republicans are notably split on the issue of banning mifepristone nationwide (52% support, 48% oppose), while a majority (57%) of Republicans support laws criminalizing health care providers mailing abortion pills to patients in states with abortion bans.
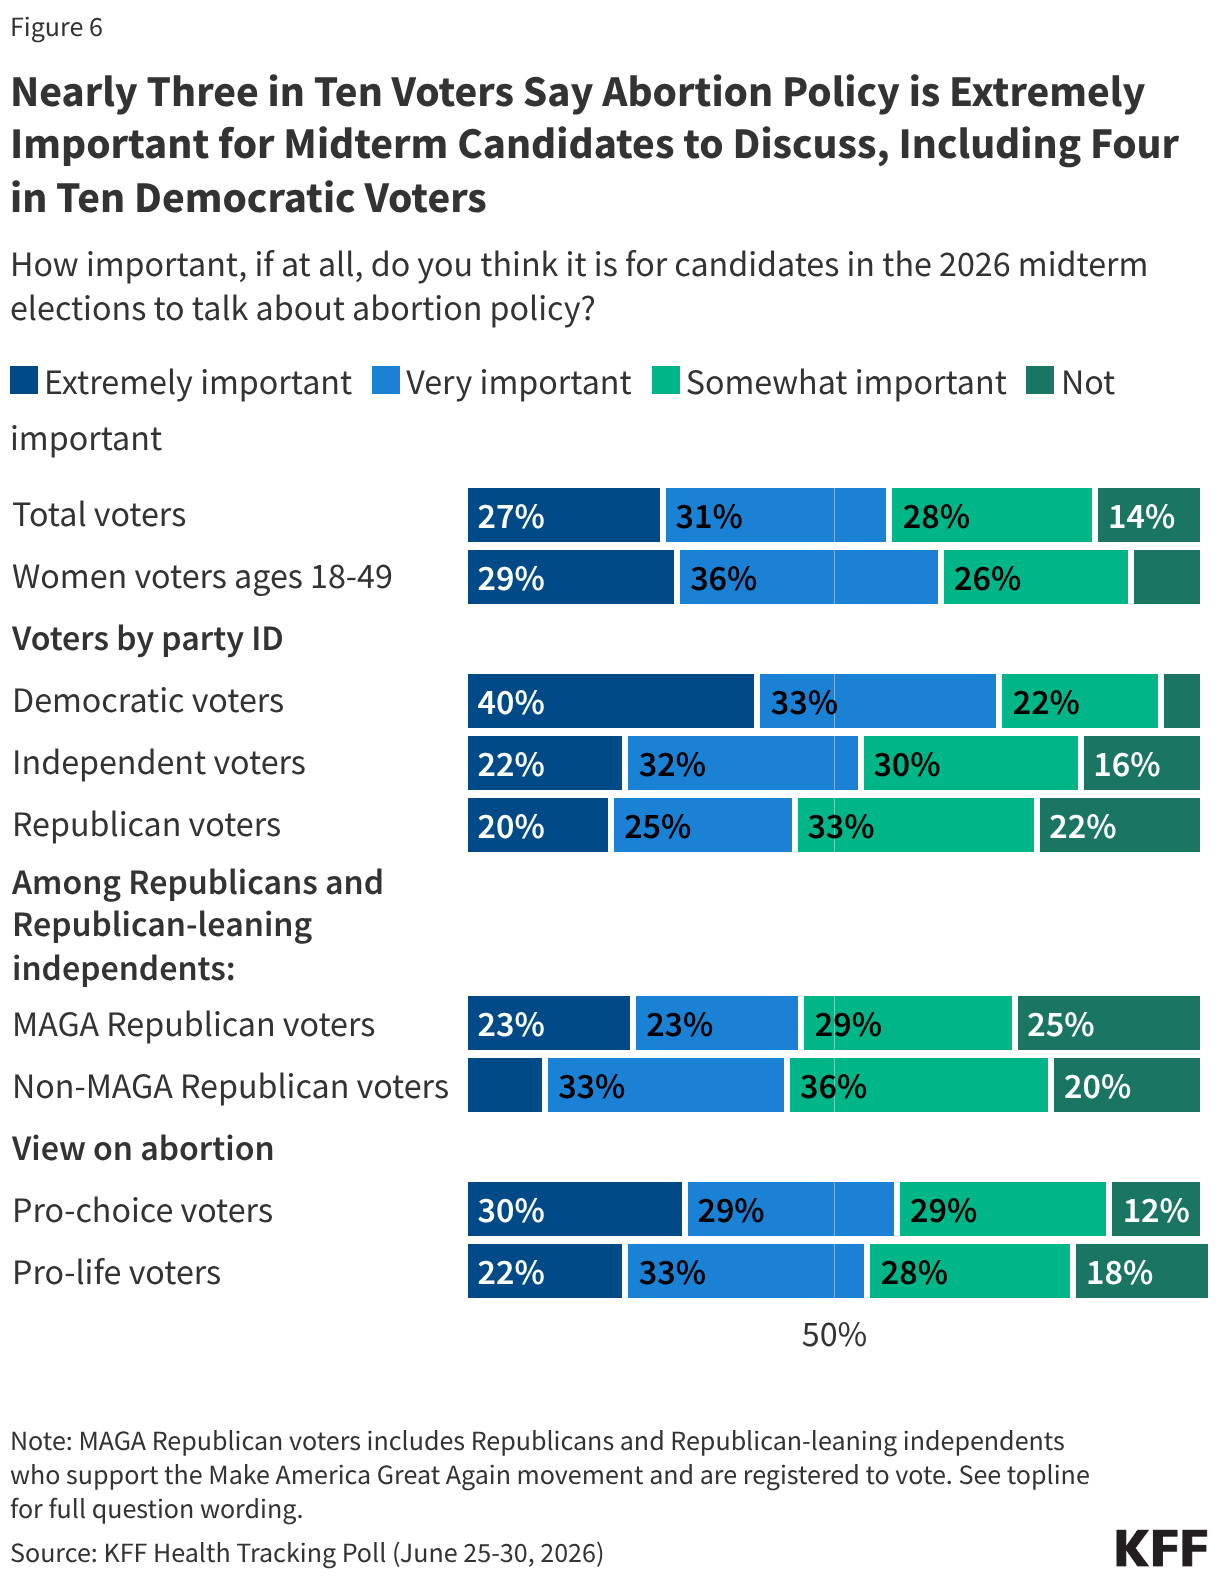
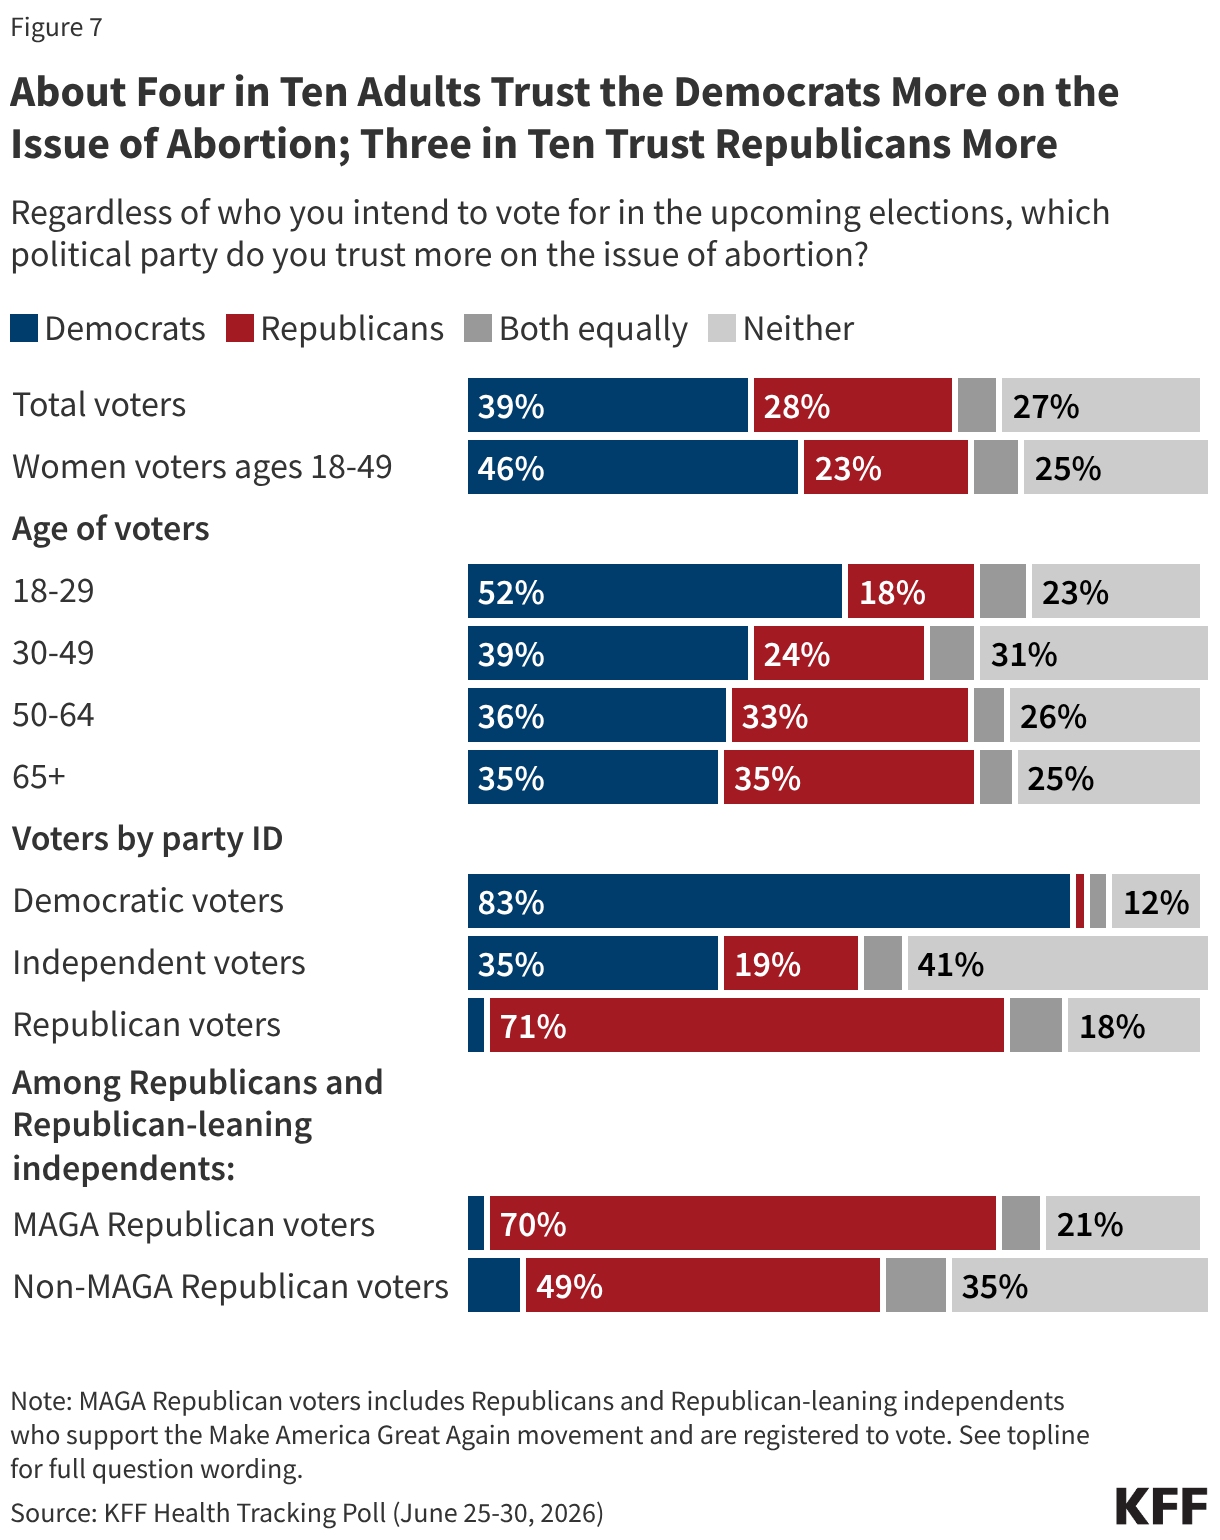
  • While health costs and the future of government health programs are key health issues for voters in the upcoming midterm elections, a majority of voters (57%) say it is “extremely” or “very important” for candidates to discuss abortion policy. Since the Dobbs decision, abortion policy remains a core issue for Democratic voters. Four in ten Democratic voters say abortion policy is “extremely important” for 2026 midterm candidates to talk about, compared to fewer independent (22%) and Republican (20%) voters. The Democratic Party has the advantage over the Republican Party when it comes to which political party voters trust more on the issue of abortion (39% vs. 28%, respectively), though nearly three in ten (27%) voters say they trust neither party on this issue. Among independent voters, the Democratic Party has the edge over the Republican Party (35% vs. 19%), though four in ten say they trust neither party on the issue.

Sizeable Shares of the Public Are Unaware of Mifepristone’s Prevalence and Safety

Mifepristone, commonly known as the abortion pill, is one of two drugs that are used in medication abortion, the most common abortion method in the United States. While mifepristone has been approved by the FDA for over 25 years and has a longstanding safety record, Congressional Republicans and anti-abortion groups continue to call into question the safety of the abortion pill. The latest KFF Health Tracking Poll finds six in ten (60%) adults have heard of the abortion medication mifepristone, including two-thirds (66%) of women of reproductive age (ages 18 to 49). Public awareness of mifepristone has risen sharply since the overturning of Roe v. Wade and the lawsuits and public scrutiny of the abortion pill that followed, increasing from 31% in January 2023 to about six in ten since then.

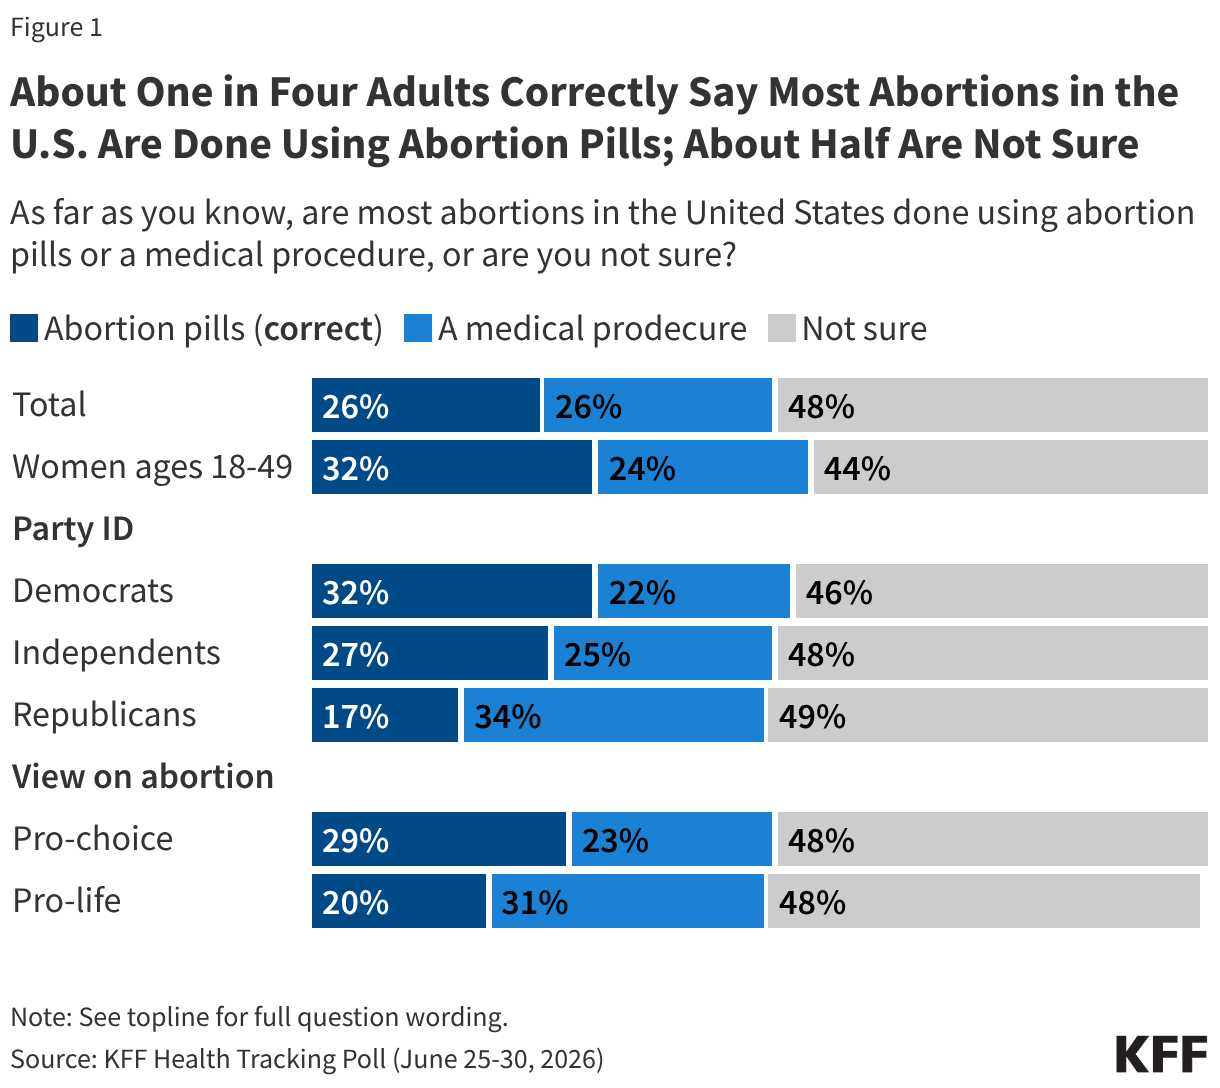
Despite increased awareness of mifepristone, the public is still largely unaware that most abortions in the U.S. are done by taking abortion pills. About one-quarter of adults (26%) correctly identify abortion pills as the most common way abortions are administered in the United States, while another quarter (26%) incorrectly say medical procedures are the most common, and nearly half (48%) say they are not sure. Democrats, independents, women of reproductive age, and adults who identify as “pro-choice” are most likely to correctly say most abortions in the U.S. are done using abortion pills. Yet, even among these groups, about half say they are not sure how most abortions in the U.S. are provided.

Stacked bar chart showing share of adults who believe most abortions in the United States are done using abortion pills, a medical procedure, or are unsure of the correct answer. Results shown by total, women of reproductive age, party, and view on abortion.

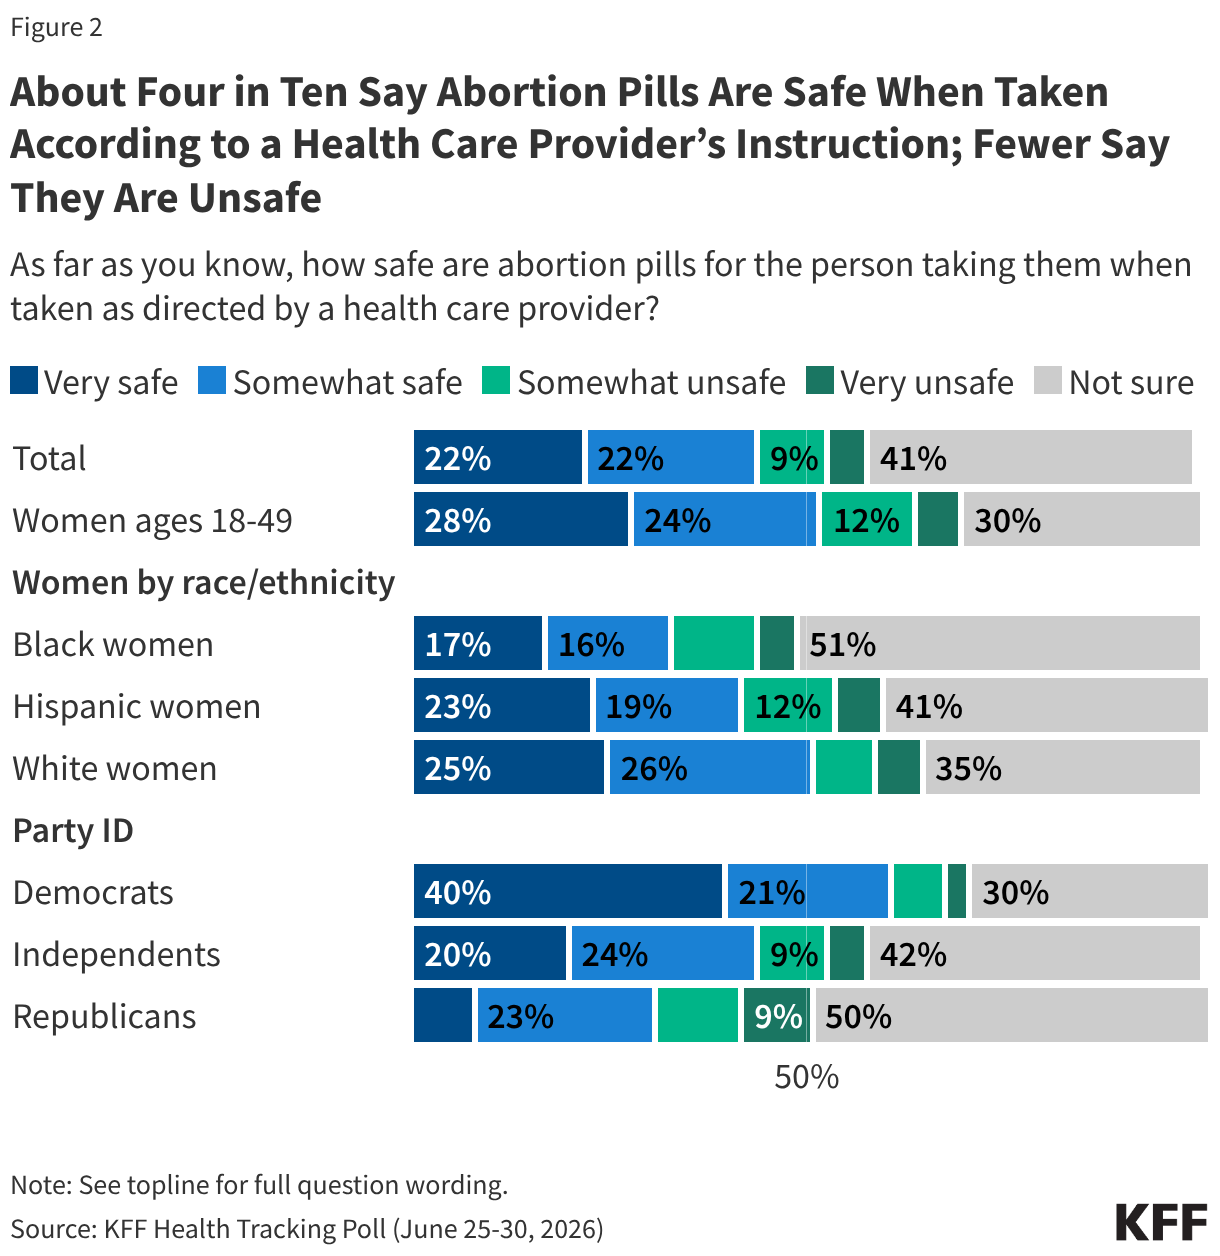
A large share of the public is unaware of the abortion medication’s longstanding safety record. Less than half (44%) of adults say abortion pills are safe when taken according to a health care provider’s instruction, about three times larger than the share who say they are unsafe (15%). Still, four in ten (41%) adults are “not sure” about the safety of abortion pills when administered according to a health care provider’s instruction.

Similar shares of adults overall say abortion pills are safe compared to last year (42% in November 2025). Among women ages 18 to 49, the group who would be most directly impacted by changes to the availability of mifepristone, about half (52%) say abortion pills are safe when taken as directed by a health care provider, a share that has increased from four in ten (41%) last November. Currently, one in five (19%) women ages 18-49 say they are not safe and three in ten are not sure of their safety.

Looking at women across racial and ethnic groups, Black women are less likely than White women to say abortion pills are safe (33% vs. 51%) and more likely than White women to say they are unsure how safe they are (51% vs. 35%). Among Hispanic women, about four in ten (42%) say abortion pills are safe, while a similar share (41%) say they are unsure.

Partisans differ in their assessment of the safety of mifepristone, with about six in ten Democrats (61%) saying medication abortion pills are “very” or “somewhat safe,” compared to about four in ten (44%) independents and three in ten Republicans. Larger shares of independents (42%) and Republicans (50%) than Democrats (30%) say they are not sure whether abortion pills are safe.

Stacked bar chart showing share of adults who believe abortion bills are very safe, somewhat safe, somewhat unsafe, very unsafe, or are unsure of the correct answer. Results shown by total, women of reproductive age, and party.

Public Divides Over Motives Behind FDA Review of Mifepristone and Ability to Conduct a Scientific Review

Last September, Health and Human Services Secretary Robert F. Kennedy Jr. and the FDA Commissioner at the time—Dr. Marty Makary—wrote to Republican state attorneys general in response to states’ concerns about mifepristone, announcing the FDA would conduct another review of the abortion pill’s safety. This new review has now begun and FDA officials are investigating whether the abortion pill’s current Risk Evaluation and Mitigation Strategy (REMS) is “sufficient to protect women from unstated risks” following the 2023 update that removed the in-person dispensing requirement and therefore made the drug accessible through telehealth. Depending on the safety review’s conclusions, the FDA could restrict mifepristone access, potentially limiting its availability through telehealth and mail, limiting the ability of advance practice clinicians from prescribing the medication, or removing pharmacies as authorized dispensers.

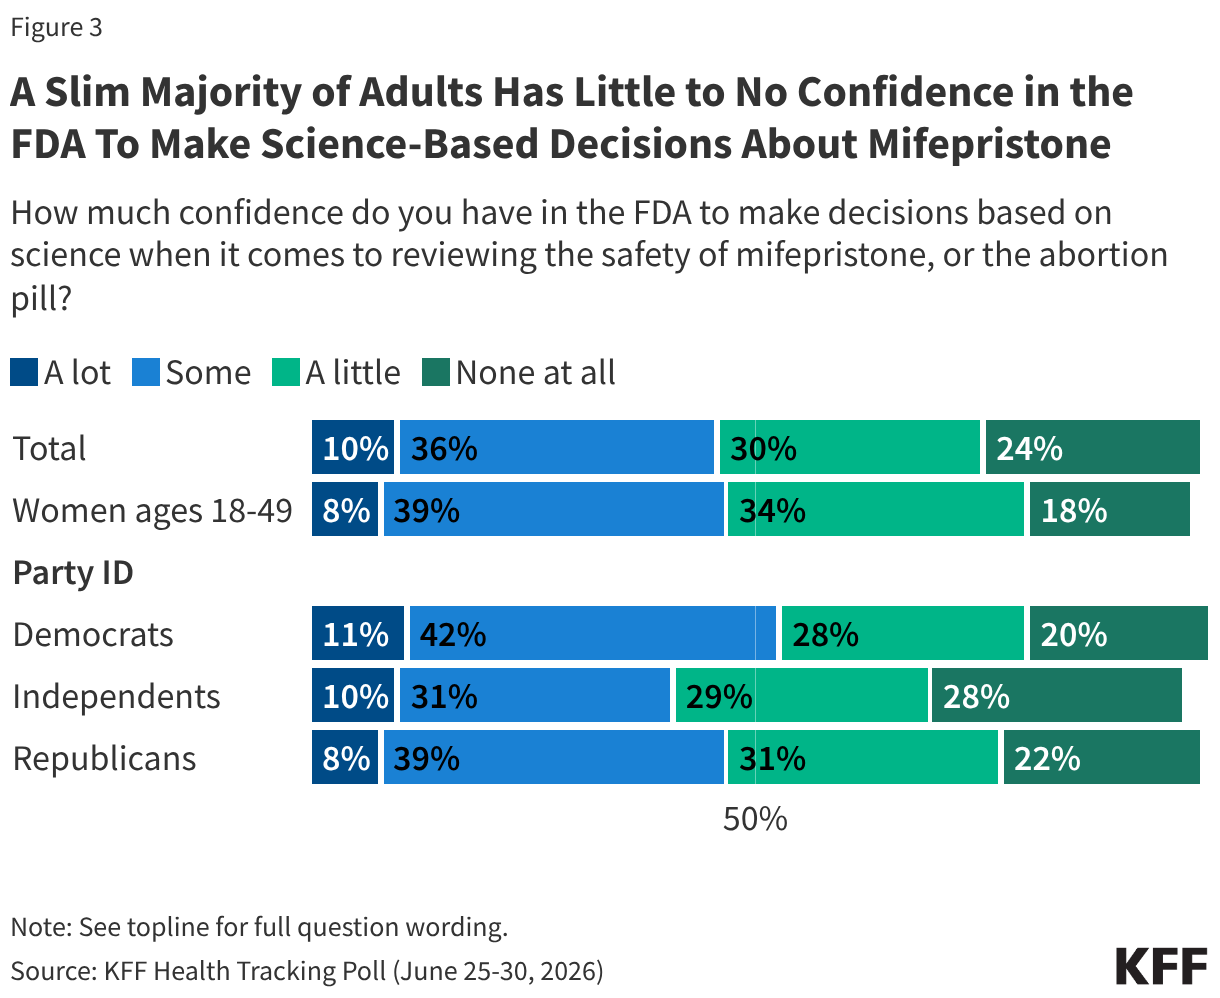
The latest KFF Health Tracking Poll finds a slim majority (54%) of the public has little to no confidence in the FDA to make decisions based on science when it comes to reviewing the abortion pill’s safety—including one in four (24%) who say they have no confidence “at all.” Fewer than half (46%) have “a lot” (10%) or “some” (36%) confidence. Among women of reproductive age, about half (52%) say they have little to no confidence, while 47% say they have at least some confidence. This limited trust is consistent with KFF’s Health Information and Trust research, which has found less than half of adults have confidence in the FDA’s ability to fulfill core responsibilities, such as making recommendations about childhood vaccine schedules and ensuring the safety and effectiveness of vaccines.

Across partisans, about half of Democrats and Republicans say they have little or no confidence (47% of Democrats; 53% of Republicans) in the FDA to make decisions based on science when evaluating the safety of mifepristone and similar shares say they have least some confidence (53% of Democrats; 47% of Republicans). Among independents, most (57%) say they have little to no confidence at all in the FDA in this regard.

Stacked bar chart showing share of adults who believe abortion bills are very safe, somewhat safe, somewhat unsafe, very unsafe, or are unsure of the correct answer. Results shown by total, women of reproductive age, and party.

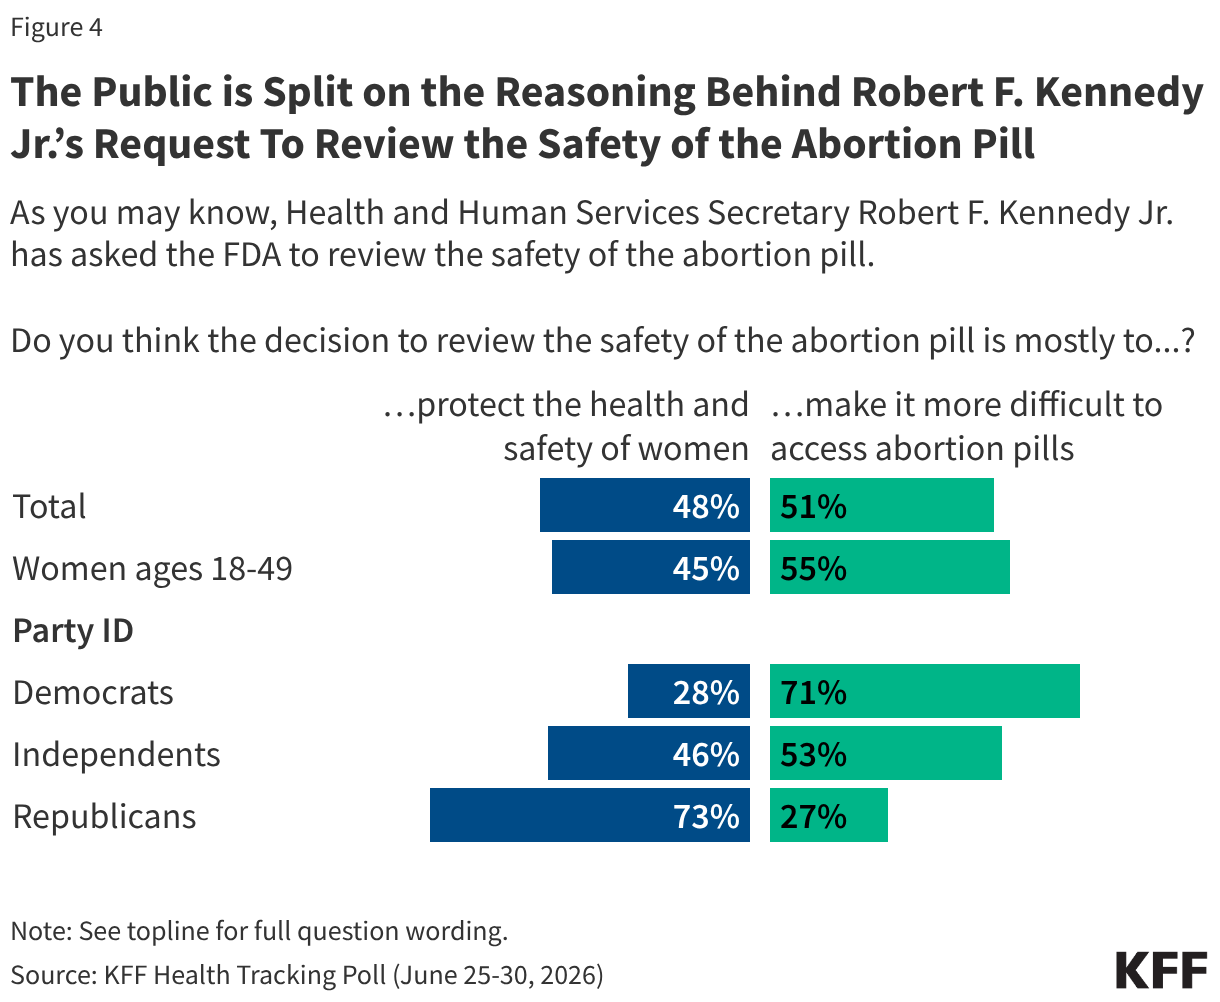
When asked about the motivation behind Secretary Kennedy’s request to the FDA to review the safety of the abortion pill, the public is split, with half (51%) saying this decision was mostly to “make it more difficult to access abortion pills,” and another half (48%) saying it was mostly to “protect the health and safety of women.”

Notably, Democrats are more likely to say the reasoning behind Kennedy’s request was to “make it more difficult to access abortion pills” (71%), while Republicans are more likely to say it was to “protect the health and safety of women” (73%). Independents are split with about half saying the decision was to make abortion access more difficult (53%) and half saying it was to protect women’s safety (47%).

Women ages 18 to 49 are also divided on the motivation behind Secretary Kennedy’s request, with about half saying his call to review mifepristone was to “make it more difficult to access abortion pills” (55%) and another half saying it was to “protect the health and safety of women” (45%).

Split bar chart showing share of adults who believe RFK Jr.'s call for an FDA review of mifepristone is to protect the health and safety of women versus make it more difficult to access abortion pills. Results shown by total, women of reproductive age, and party.

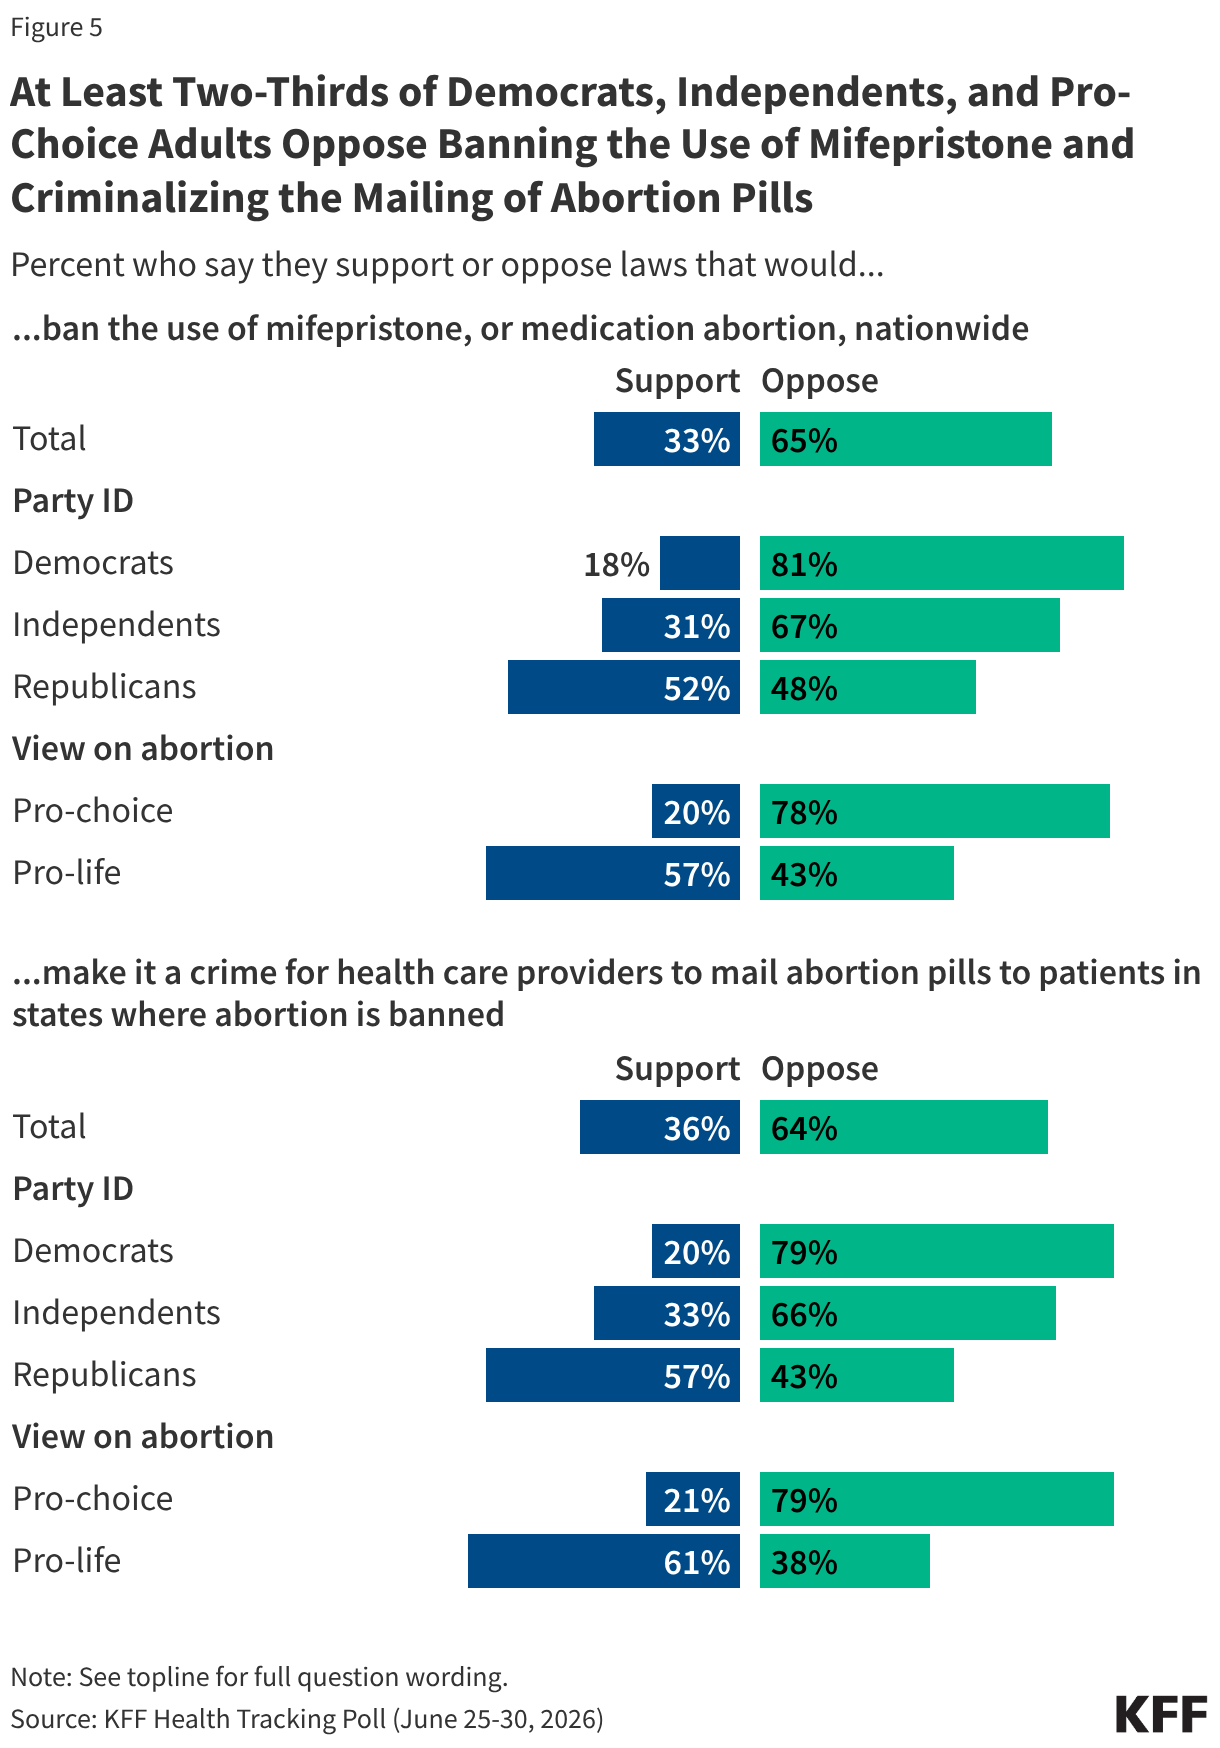
The latest KFF Health Tracking Poll finds majorities oppose laws that would place further restrictions on medication abortion. Around two-thirds of adults say they oppose banning the use of mifepristone, or medication abortion, nationwide (65%) and a similar share oppose making it a crime for health care providers to mail abortion pills to patients in states where abortion is banned (64%).

Eight in ten Democrats (81%) and two-thirds of independents (67%) say they oppose banning mifepristone entirely. However, Republicans are split in their views, with half (52%) saying they support laws that would ban the abortion pill nationwide while a similar share (48%) say they are opposed. And, while large majorities of Democrats (79%) and independents (66%) oppose laws making it a crime to mail abortion pills to patients in states with abortion bans, a majority (57%) of Republicans support such laws while 43% are opposed.

Unsurprisingly, about eight in ten adults who identify as pro-choice oppose the restrictive abortion laws asked about in this KFF Health Tracking Poll (78% banning mifepristone; 79% criminalizing the mailing of abortion pills to patients in states with abortion bans). Among those who identify as pro-life, majorities say they support these laws (57% and 61%, respectively), though sizeable shares—about four in ten—say they would oppose laws banning mifepristone nationwide (43%) and criminalizing the mailing of abortion pills to abortion-banned states (38%).

Split bar chart showing share of adults who support versus oppose laws that ban the use of mifepristone or medication abortion nationwide and laws that make it a crime for health care providers to mail abortion pills to patients in states where abortion is banned. Results shown by total and party.

Voters’ Attitudes Toward Abortion in the Upcoming Midterm Elections

While health costs and the future of government health programs such as Medicare and Medicaid are the health issues taking center stage in this election, a majority of voters (57%) say it is “extremely” (27%) or “very important” (31%) for candidates to talk about abortion policy. Looking at voters by views on abortion, slightly larger shares of pro-choice voters say abortion is extremely important for 2026 midterm candidates to discuss compared to their pro-life counterparts (30% vs. 22%).

Previous election-related polling at KFF has found that, since the Dobbs decision, voters who view abortion policy as an important issue are disproportionately Democrats, and this election is no exception. Three-quarters (73%) of Democratic voters say abortion policy is important for 2026 midterm candidates to talk about, including four in ten who say it is “extremely important.” Notably, the share who say abortion policy is “extremely important” is consistent among Democratic voters, regardless of whether those voters live in states where abortion is either banned or limited (40%) or where abortion is available (39%). In contrast, fewer independent (22%) and Republican (20%) voters say abortion policy is extremely important for midterm candidates to discuss.

Among Republican and Republican-leaning independent voters who support the Make America Great Again movement, nearly one in four (23%) say abortion policy is extremely important for candidates to discuss, compared to one in ten (11%) non-MAGA-supporting Republicans and Republican-leaning independents who say the same. About two-thirds of MAGA Republicans identify as pro-life (63%), while about four in ten (44%) non-MAGA supporting Republicans identify as pro-choice.

Stacked bar chart showing share of adults who believe most abortions in the United States are done using abortion pills, a medical procedure, or are unsure of the correct answer. Results shown by total, women of reproductive age, party, and view on abortion.

The Democratic Party has the advantage over Republicans when it comes to which political party voters trust more on the issue of abortion (39% vs. 28%, respectively), though nearly three in ten (27%) voters say they trust neither party on this issue. Women voters ages 18 to 49 and younger voters (ages 18 to 29) are notably among the most likely to trust the Democratic Party more (46% and 52%, respectively).

Unsurprisingly, voters are largely split across partisan identification when it comes to which political party they trust more on the issue of abortion. Among independent voters, the Democratic Party has the edge over the Republican Party (35% vs. 19%), though four in ten (41%) say they trust neither party on the issue.

Stacked bar chart showing share of adults who believe most abortions in the United States are done using abortion pills, a medical procedure, or are unsure of the correct answer. Results shown by total, women of reproductive age, party, and view on abortion.

This KFF Health Tracking Poll/KFF Tracking Poll on Health Information and Trust was designed and analyzed by public opinion researchers at KFF. The survey was conducted June 25 – June 30, 2026, online and by telephone among a nationally representative sample of 1,321 U.S. adults in English (n=1,238) and in Spanish (n=83). The sample includes 1,015 adults (n=69 in Spanish) reached through the SSRS Opinion Panel either online (n=990) or over the phone (n=25). The SSRS Opinion Panel is a nationally representative probability-based panel where panel members are recruited randomly in one of two ways: (a) Through invitations mailed to respondents randomly sampled from an Address-Based Sample (ABS) provided by Marketing Systems Groups (MSG) through the U.S. Postal Service’s Computerized Delivery Sequence (CDS); (b) from a dual-frame random digit dial (RDD) sample provided by MSG. For the online panel component, invitations were sent to panel members by email followed by up to three reminder emails.

Another 306 (n=14 in Spanish) adults were reached through random digit dial telephone sample of prepaid cell phone numbers obtained through MSG. Phone numbers used for the prepaid cell phone component were randomly generated from a cell phone sampling frame with disproportionate stratification aimed at reaching Hispanic and non-Hispanic Black respondents. Stratification was based on incidence of the race/ethnicity groups within each frame. Among this prepaid cell phone component, 142 were interviewed by phone and 164 were invited to the web survey via short message service (SMS).

Respondents in the prepaid cell phone sample who were interviewed by phone received a $15 incentive via a check received by mail or an electronic gift card incentive. Respondents in the prepaid cell phone sample reached via SMS received a $10 electronic gift card incentive. SSRS Opinion Panel respondents received a $5 electronic gift card incentive (some harder-to-reach groups received a $10 electronic gift card). In order to ensure data quality, cases were removed if they failed two or more quality checks: (1) attention check questions in the online version of the questionnaire, (2) had over 30% item non-response, or (3) had a length less than one quarter of the mean length by mode. Based on this criterion, 1 case was removed.

The combined cell phone and panel samples were weighted to match the sample’s demographics to the national U.S. adult population using data from the Census Bureau’s 2025 Current Population Survey (CPS), September 2023 Volunteering and Civic Life Supplement data from the CPS, and the 2026 KFF Benchmarking Survey with ABS and prepaid cell phone samples. The demographic variables included in weighting for the general population sample are gender, age, education, race/ethnicity, region, civic engagement, frequency of internet use and political party identification. The weights account for differences in the probability of selection for each sample type (prepaid cell phone and panel). This includes adjustment for the sample design and geographic stratification of the cell phone sample, within household probability of selection, and the design of the panel-recruitment procedure.

The margin of sampling error including the design effect for the full sample is plus or minus 3 percentage points. Numbers of respondents and margins of sampling error for key subgroups are shown in the table below. For results based on other subgroups, the margin of sampling error may be higher. Sample sizes and margins of sampling error for other subgroups are available on request. Sampling error is only one of many potential sources of error and there may be other unmeasured error in this or any other public opinion poll. KFF public opinion and survey research is a charter member of the Transparency Initiative of the American Association for Public Opinion Research.

GroupN (unweighted)M.O.S.E.
Total1,321± 3 percentage points
Total voters1,055± 4 percentage points
   
Democrats426± 6 percentage points
Independents439± 6 percentage points
Republicans358± 6 percentage points
   
Democratic voters372± 6 percentage points
Independent voters316± 7 percentage points
Republican voters312± 7 percentage points
   
Women ages 18-49414± 6 percentage points

Medicare’s Proposed Cut to 340B Drug Payments Would Hit Safety-Net Hospitals While Benefiting For-Profit Hospitals

Published: Jul 29, 2026

The recently proposed 2027 Medicare Hospital Outpatient Perspective Payment System (OPPS) rule from the Centers for Medicare & Medicaid Services (CMS) includes a proposal to reduce Medicare’s reimbursement for 340B drugs. The proposal would reduce reimbursement for 340B drugs from average sales price (ASP) plus 6% (what Medicare generally pays for Part B outpatient drugs administered by providers) to ASP minus 33.4%, a 37% reduction. CMS indicated that this change would better align Medicare reimbursement with hospitals’ costs of acquiring 340B drugs.

The 340B Drug Pricing Program requires drug manufacturers participating in Medicaid to sell outpatient drugs to eligible nonprofit and government providers at a substantial discount, allowing providers to earn larger profits when being reimbursed for 340B drugs. The intent of the program is to support providers, such as certain disproportionate share hospitals and federally qualified health clinics, that care for low-income and other underserved populations. Critics have raised concerns that the 340B program, which has grown substantially over time, is not well-targeted; that savings from the program are not shared with patients; and that the program incentivizes hospitals to acquire clinics and physician practices in order to extend 340B discounts to those settings, enabling them to generate more revenue. Supporters of the program say that revenues generated by the difference between Medicare (and other payer) reimbursement for 340B drugs and the discounted price help 340B providers care for underserved populations and invest in operations.

CMS based the amount of the proposed payment reduction on a cost acquisition survey of 340B drugs completed by hospitals in early 2026. This proposed change revives an earlier effort by CMS to reduce Medicare payments for 340B drugs that was implemented in 2018 under the first Trump administration, but the Supreme Court overturned that rule in 2022 because the agency had not first conducted a cost acquisition survey. If finalized, CMS’s proposed Medicare 340B payment reduction would take effect on January 1, 2027, and would have disparate effects on different types of hospitals, as described more below.

CMS’s proposed cut to 340B drug reimbursement would reduce Medicare spending on 340B drugs by an estimated $4.85 billion in 2027, while increasing spending on non-drug outpatient services by the same amount because of budget neutrality requirements. Under federal law, CMS is generally required to maintain the same amount of aggregate spending through OPPS regardless of reimbursement changes (i.e., maintain budget neutrality). Based on this requirement, CMS proposed an 8.44% across-the-board increase in payments for non-drug outpatient services covered under the OPPS, which the agency estimates will offset the impact of cuts to spending on 340B drugs in 2027.

The budget neutrality requirement means that savings from reductions in 340B payments to 340B hospitals would be redistributed to both 340B and non-340B hospitals through higher payments for non-drug outpatient services. Similarly, Medicare beneficiaries would face lower cost sharing on 340B drugs (e.g., based on 20% coinsurance applied to a lower amount) but higher cost sharing for non-drug outpatient hospital services. CMS estimates that Medicare beneficiaries who use 340B drugs would save $1.15 billion in total in 2027, but cost sharing would increase for beneficiaries who use non-drug outpatient hospital services based on Medicare’s proposed 8.44% payment increase.

Proposed cuts would reduce revenues among safety-net hospitals while increasing revenues among for-profit hospitals, among other differences. For 340B hospitals, total Medicare revenues would decrease or increase depending on how reliant they are on revenues from 340B drugs versus non-drug outpatient services, but non-340B hospitals would experience revenue increases only based on the higher payment rate for non-drug outpatient services. CMS’s proposal to reduce reimbursement for 340B drugs would exempt rural sole community hospitals (SCHs) (rural hospitals that are the only source of short-term, acute inpatient care in a region), children’s hospitals, and PPS-exempt cancer hospitals. Changes would not affect hospitals that are not reimbursed under the OPPS, including critical access hospitals (CAHs), which make up the majority of rural hospitals.

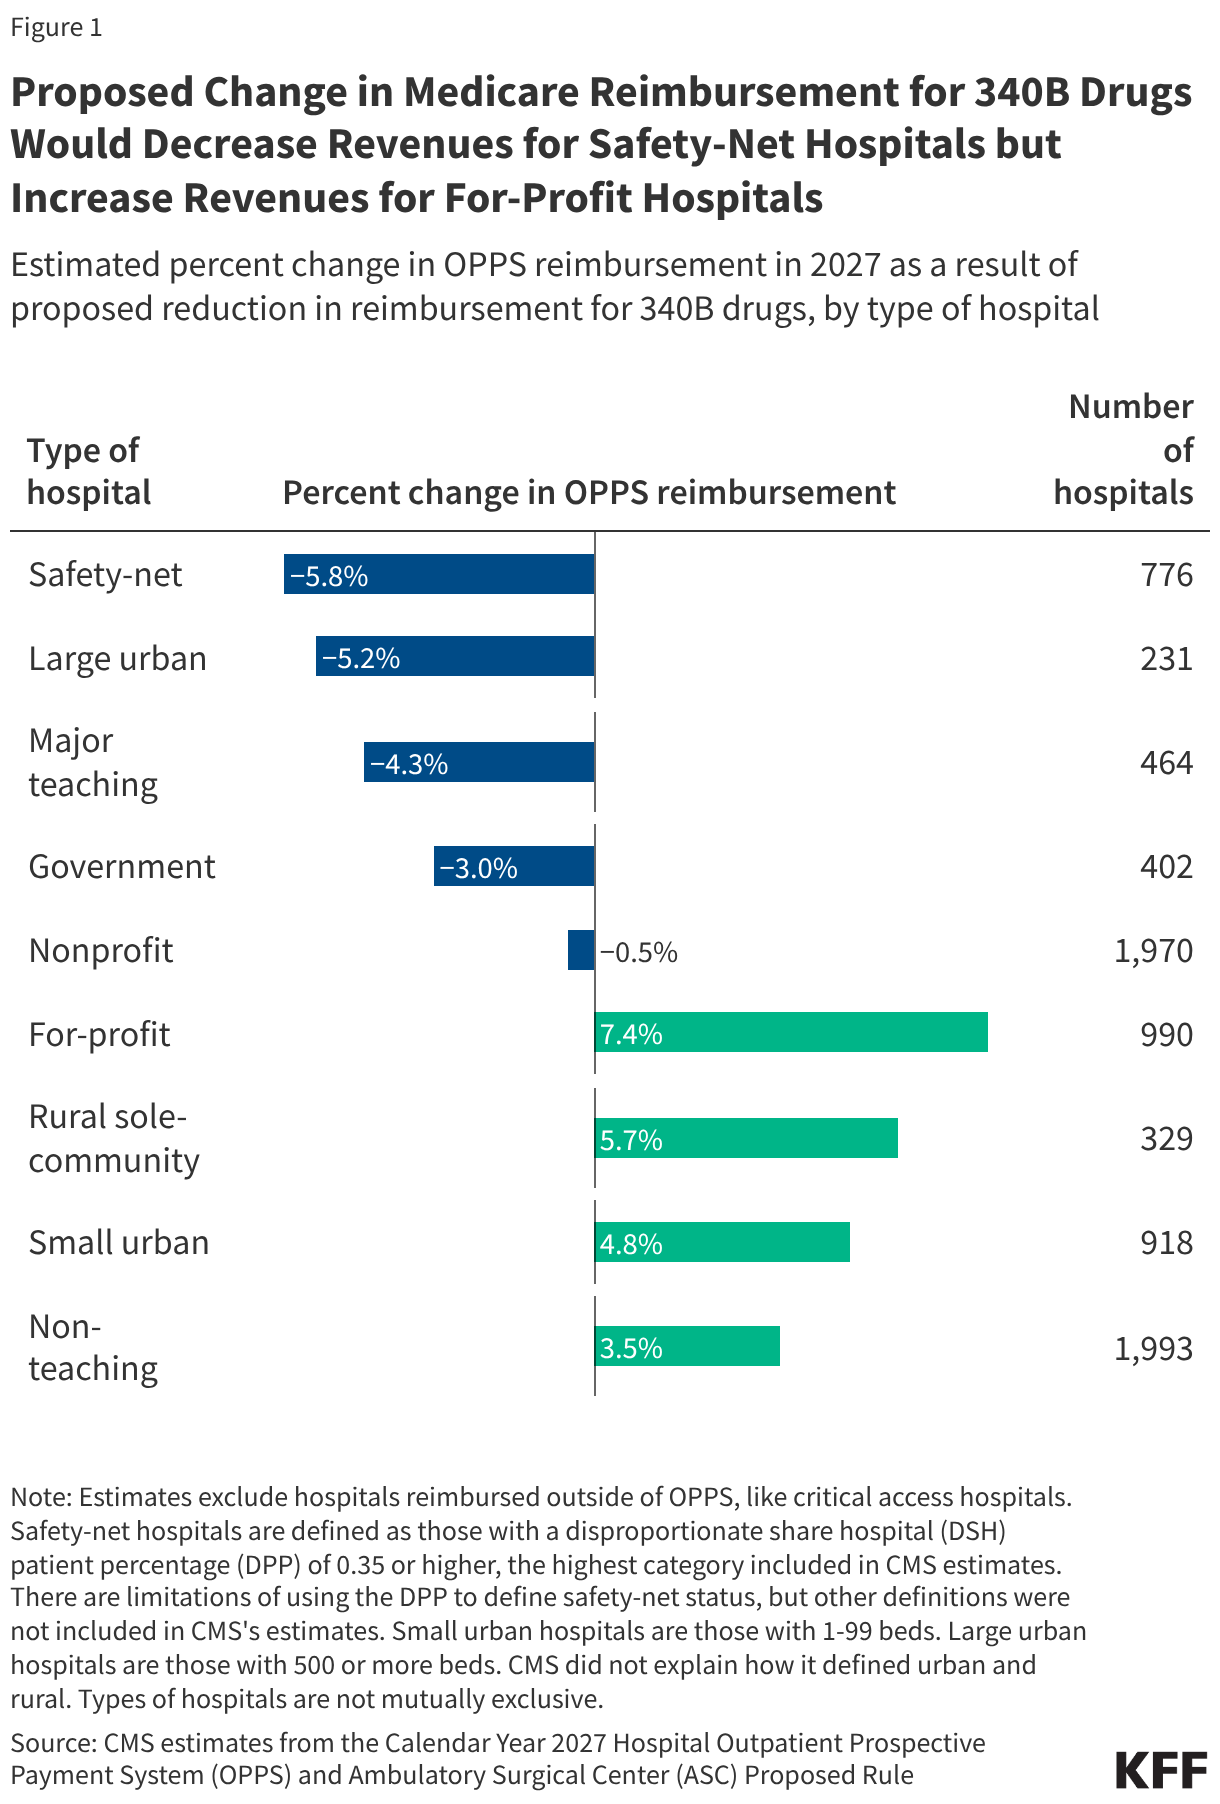
In the aggregate, some types of hospitals would lose or benefit more from these changes than others, based on estimates from CMS (Figure 1):

  • Safety-net hospitals would face a 5.8% net reduction of OPPS revenue under this proposal (see figure notes for definition of “safety-net hospitals”). Other types of hospitals would also see net reductions in OPPS revenue in the aggregate, including large urban hospitals (with 500 beds or more) (-5.2%), major teaching hospitals (-4.3%), government hospitals (-3.0%), and nonprofit hospitals (-0.5%). Some hospitals that would see the largest decrease in revenue likely fall into more than one of these categories (e.g., major teaching hospitals tend to be large urban hospitals).
  • For-profit hospitals would see a 7.4% net increase in OPPS revenues. For-profit hospitals are not eligible for the 340B program and so would only see increases in reimbursement for non-drug outpatient services. Other types of hospitals would also face net increases in Medicare OPPS reimbursement in aggregate, including rural SCHs (5.7%), small urban hospitals (with 0 to 99 beds) (4.8%), and non-teaching hospitals (3.5%). 
Proposed Change in Medicare Reimbursement for 340B Drugs Would Decrease Revenues for Safety-Net Hospitals but Increase Revenues for For-Profit Hospitals (Table)

Reductions in 340B payments could add to the financial challenges facing safety-net hospitals while increasing margins of for-profit hospitals. Safety-net hospitals have lower operating margins than average and so could have an especially difficult time absorbing any revenue losses from the 340B payment cut, while for-profit hospitals have much higher operating margins than the average hospital. Additionally, safety-net hospitals, which are particularly dependent on Medicaid revenues, are likely to be disproportionately affected by the 2025 reconciliation law, as it achieves most of its health care savings through federal Medicaid spending reductions.

The substantial growth of the 340B program in recent years has led hospitals, pharmaceutical companies, and policymakers to focus on whether and how to change the program. At the federal level, lawmakers have proposed options that would preserve or narrow the scope of the program and have proposed increasing transparency around the program, such as by requiring hospitals to report 340B savings. At the state level, some states have passed laws that would preserve the ability of hospitals to use multiple contract pharmacies to dispense 340B drugs, among other things. Other states have implemented requirements for hospitals to disclose the amount of savings generated from the 340B program (as required by Minnesota) or how those savings are spent.

Some pharmaceutical companies have attempted to start providing 340B drug discounts through a rebate model, an approach that would require hospitals to purchase 340B drugs at a non-discounted price and receive post-sale rebates after submitting claims information. These efforts have been halted by the courts due to lack of authorization from HHS, the agency that administers the 340B program. In 2025, the Trump administration attempted to implement the 340B Rebate Model Pilot Program, but a court halted the pilot after a lawsuit was filed by the hospital industry. HHS has recently requested information from stakeholders on a revised rebate model pilot.

Appendix

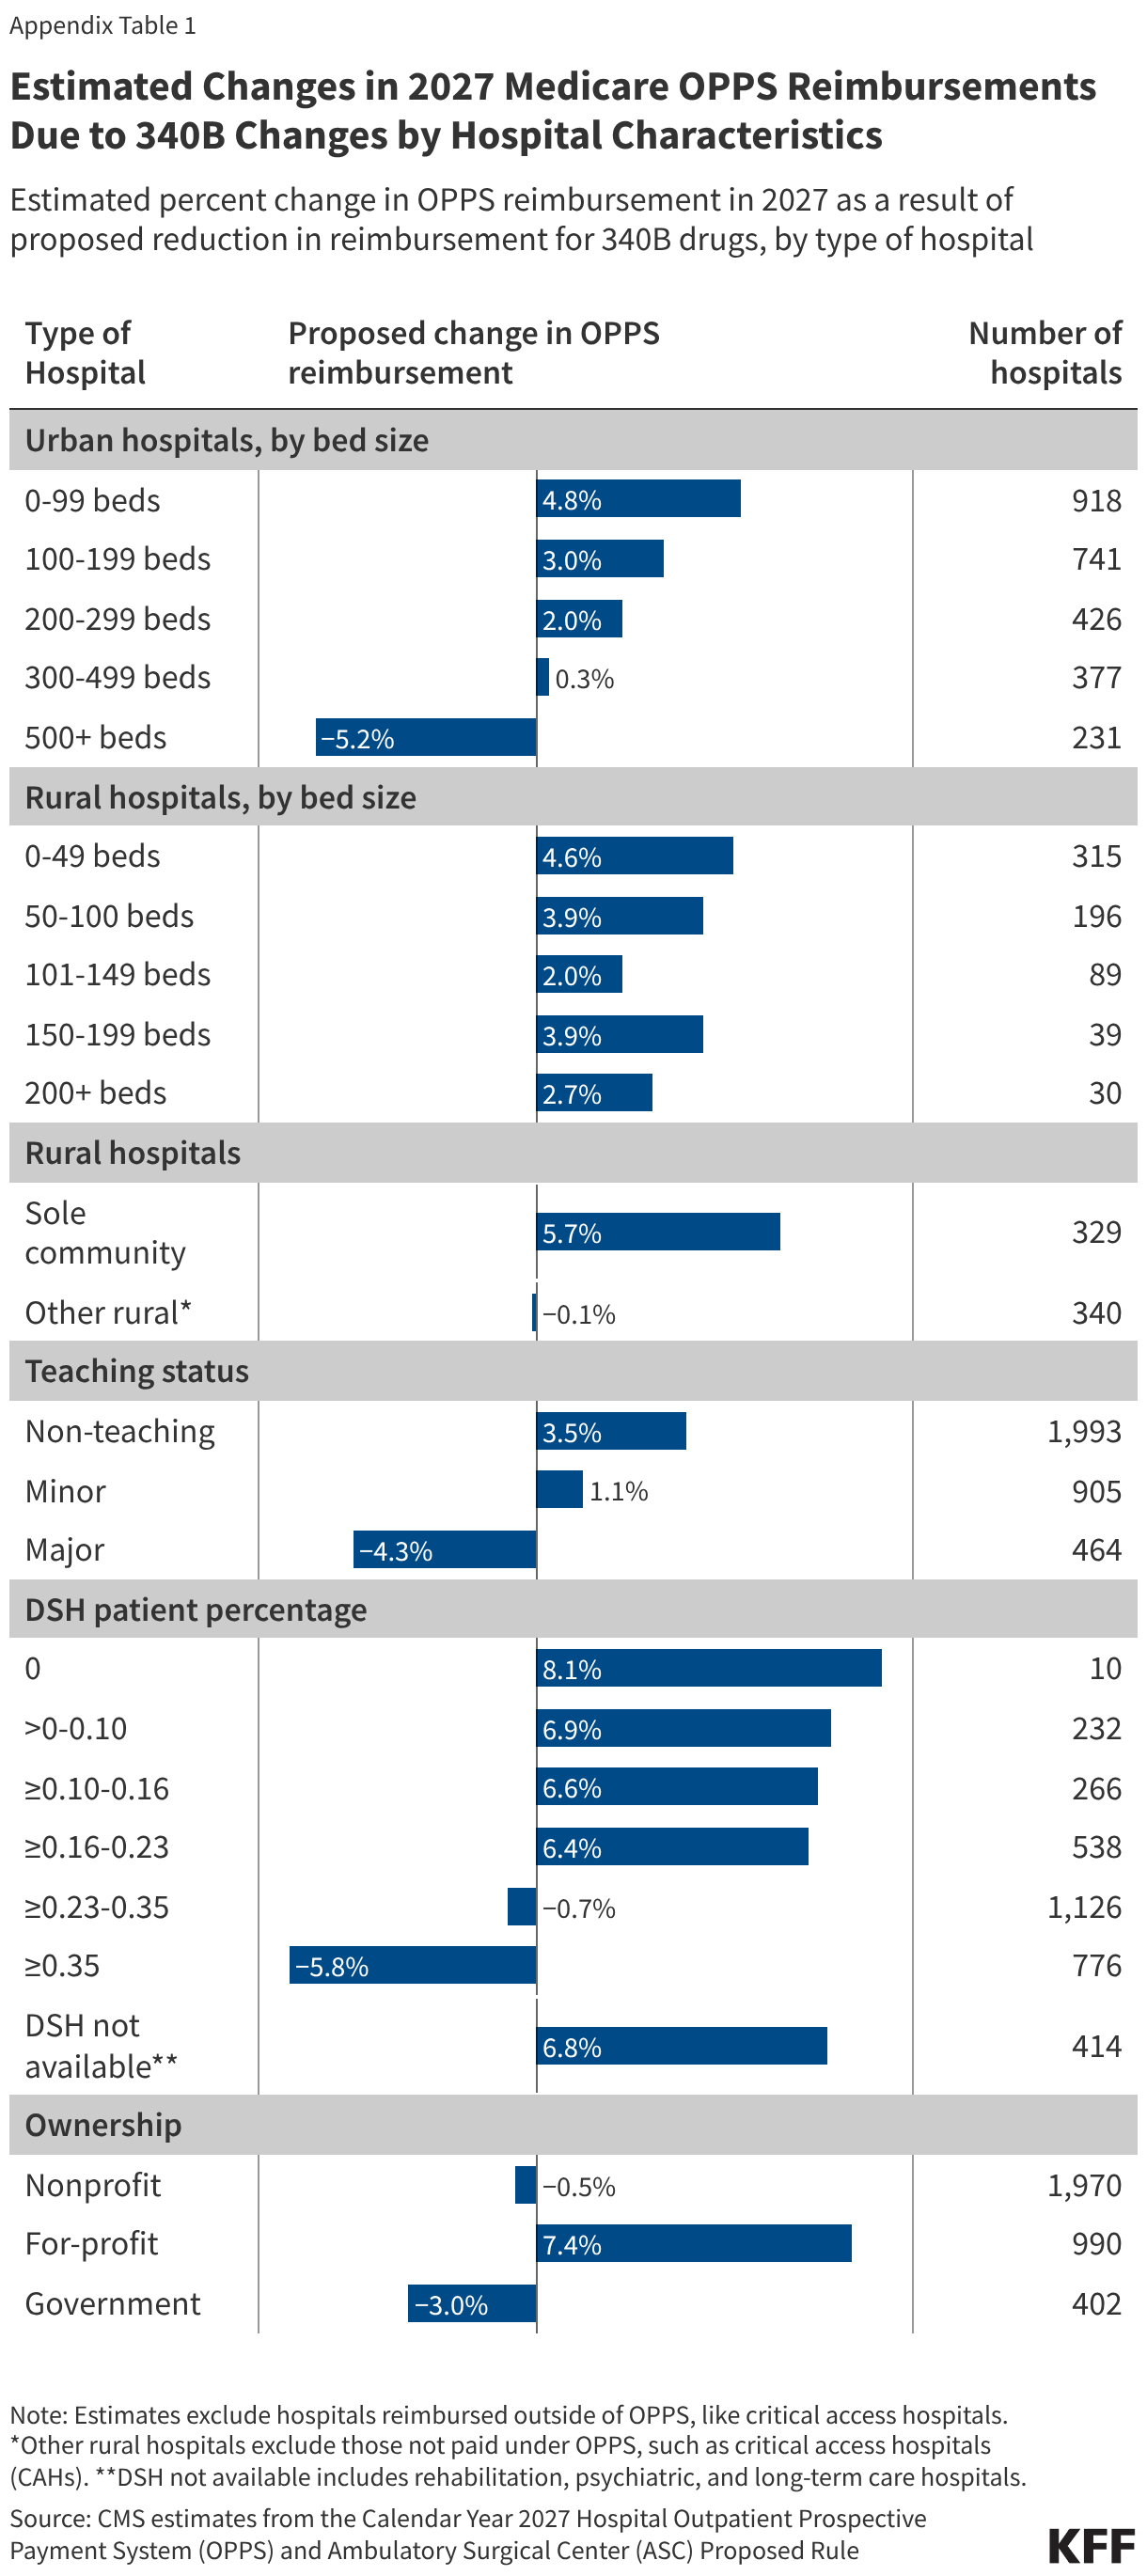
Estimated Changes in 2027 Medicare OPPS Reimbursements Due to 340B Changes by Hospital Characteristics (Table)

How Has ACA Marketplace Enrollment Changed Across States in 2026?

Published: Jul 28, 2026

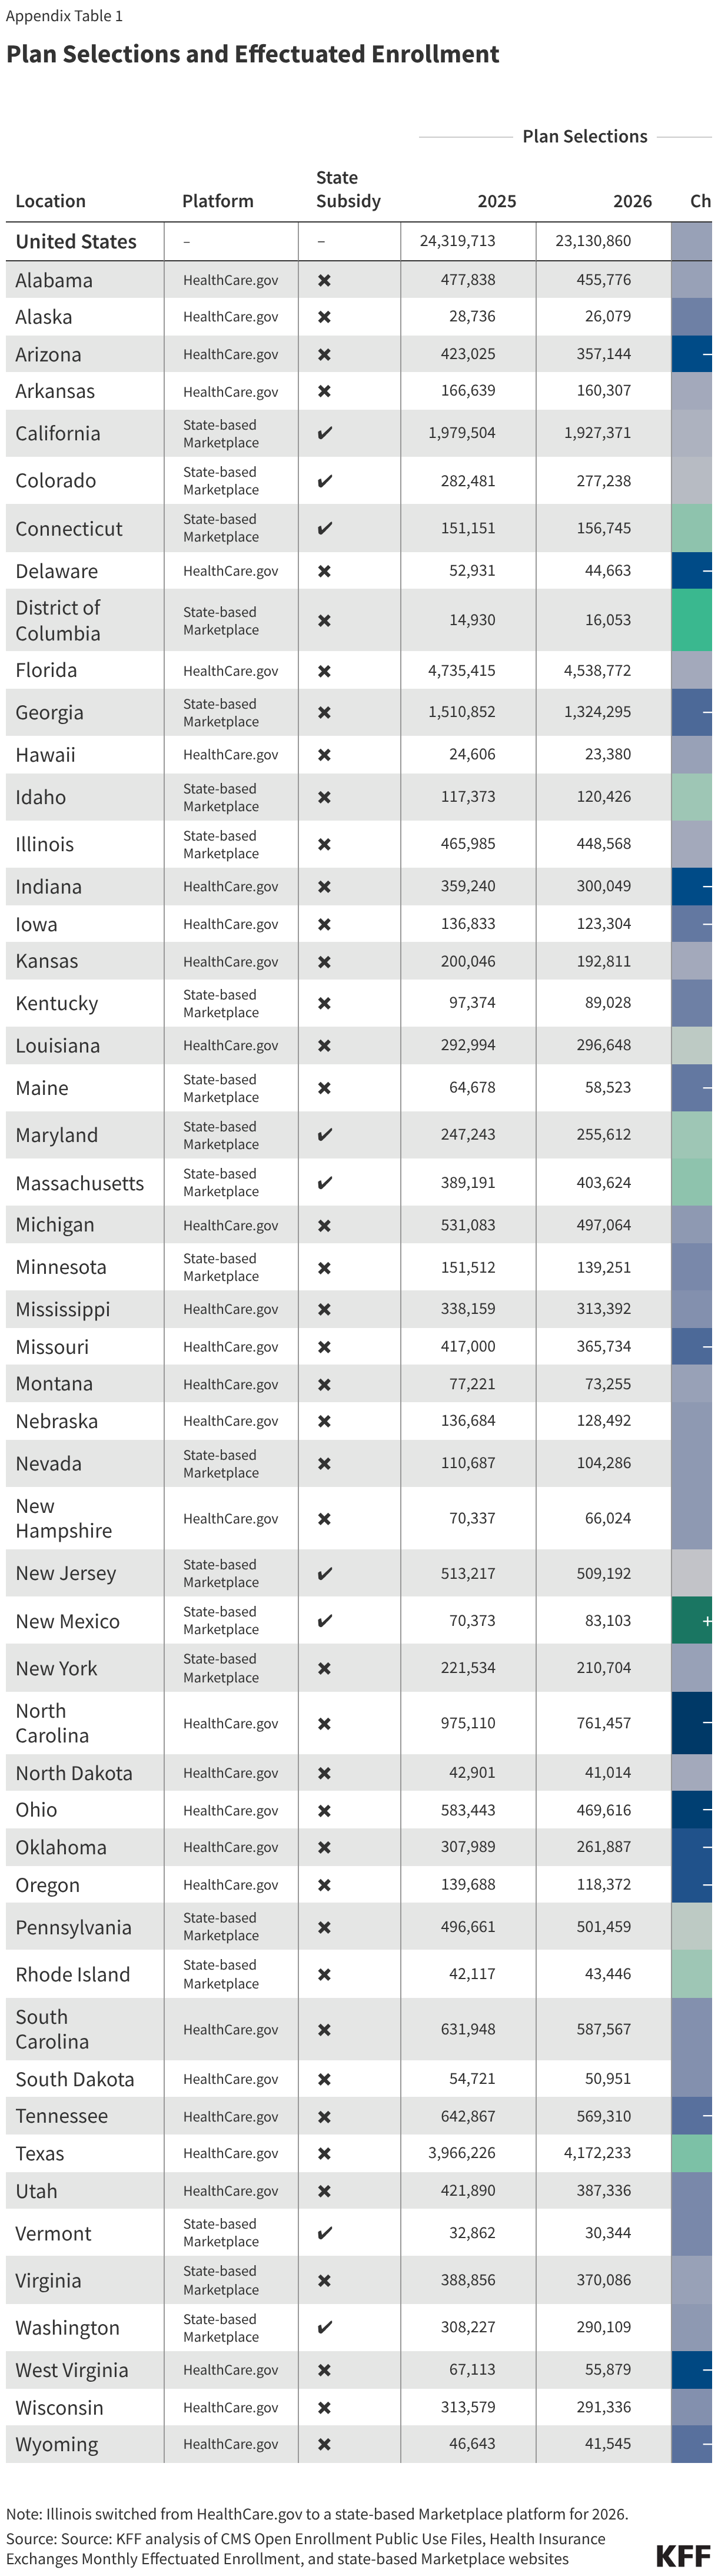
Following several years of rapid enrollment growth in the Affordable Care Act (ACA) Marketplaces that corresponded with temporary enhanced premium tax credits, enrollment fell for the first time in seven years in 2026, when those tax credits expired. The Assistant Secretary for Planning and Evaluation (ASPE) of the Department of Health and Human Services reported that enrollment declined by nearly three million people between 2025 and 2026.

Earlier federal data and analysis had focused on plan selections, or sign-ups, which decreased by about one million (5%) from last year, but plan selections do not account for enrollees who ultimately do not make their premium payments and are not covered. Effectuated enrollment is different from selection or sign-up data in that it accounts for who paid their premiums. Consumers who canceled their coverage or did not make their premium payments, resulting in termination of coverage, do not contribute to effectuated enrollment totals.

This analysis uses data from the Centers for Medicare and Medicaid Services (CMS) on effectuated enrollment in addition to Open Enrollment plan selections to examine how enrollment in the ACA Marketplaces has changed in 2026.

Key Findings

  • Every state except for New Mexico saw a drop in ACA Marketplace enrollment from 2025 to 2026. New Mexico is the only state to fully replace the expired federal enhanced premiums tax credits with state-funded subsidies.
  • State-based Marketplaces that run their own enrollment platforms, including those that partially offset the expiring federal enhanced tax credits, generally saw lower drops in enrollment (a 6% decline versus a 15% decline for states that use the federal marketplace).
  • The effectuation rate (the rate at which people who initially signed up for a plan kept their coverage by making their premium payments) was lower in 2026 than in recent years.
  • States that run their own Marketplaces, and particularly those that offered state-funded subsidies, generally saw higher-than-average effectuation rates.

February effectuated enrollment declined in 2026 to 19.2 million people (as of May 5, 2026), down from 21.8 million people in 2025, a record high enrollment (see note in Methods about 2025 total enrollment). This represents a 12% decline in enrollment year-over-year. Similarly,  KFF polling indicated about one in ten 2025 Marketplace enrollees (9%) said they became uninsured for the 2026 plan year. The decline in enrollment coincides with the expiration of the enhanced premium tax credits at the end of 2025.
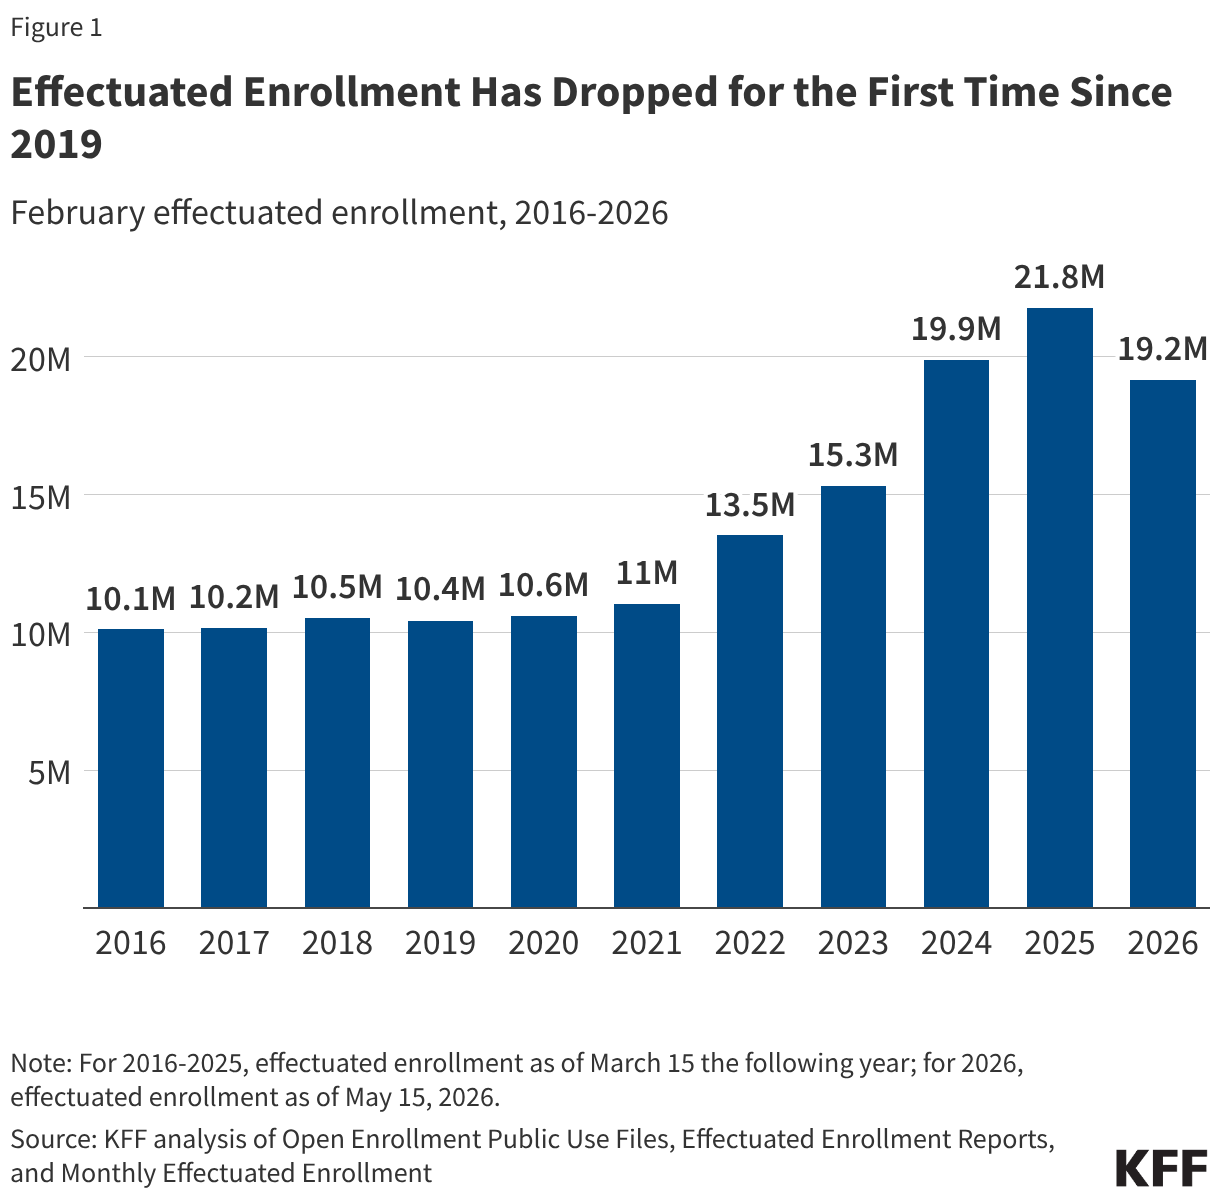
Effectuated Enrollment Has Dropped for the First Time Since 2019 (Column Chart)

While effectuated enrollment data do not capture the reasons coverage lapsed, these significant declines in enrollment correspond with rising premium payments after the expiration of enhanced premium tax credits. Without the enhanced credits, premium payments increased substantially for most subsidized enrollees, and some middle-income enrollees who previously qualified for subsidies faced the full cost of coverage for the first time. On average, premium payments net of tax credits increased by 58% for people who signed up for 2026 coverage. A 2026 KFF follow-up survey of people who had been enrolled in ACA Marketplace coverage in 2025 found that eight in 10 enrollees who made changes to their ACA coverage or became uninsured cited cost as a reason, with 17% of returning Marketplace enrollees stating they worried about being able to pay their premiums for the entirety of 2026.

As shown in Figure 2, 2026 was the first year of widespread increases in premium payments. In prior years, including before the implementation of enhanced premium tax credits, people receiving a subsidy were largely sheltered from increases in the premiums charged by insurers. This may at least in part explain why the effectuation rate in 2026 was lower than some years preceding the enhanced premium tax credits. While the drop in enrollment from 2025 to 2026 is the largest drop since the Marketplaces opened, there are still more ACA Marketplace enrollees now than there were before the enhanced premium tax credits were passed.
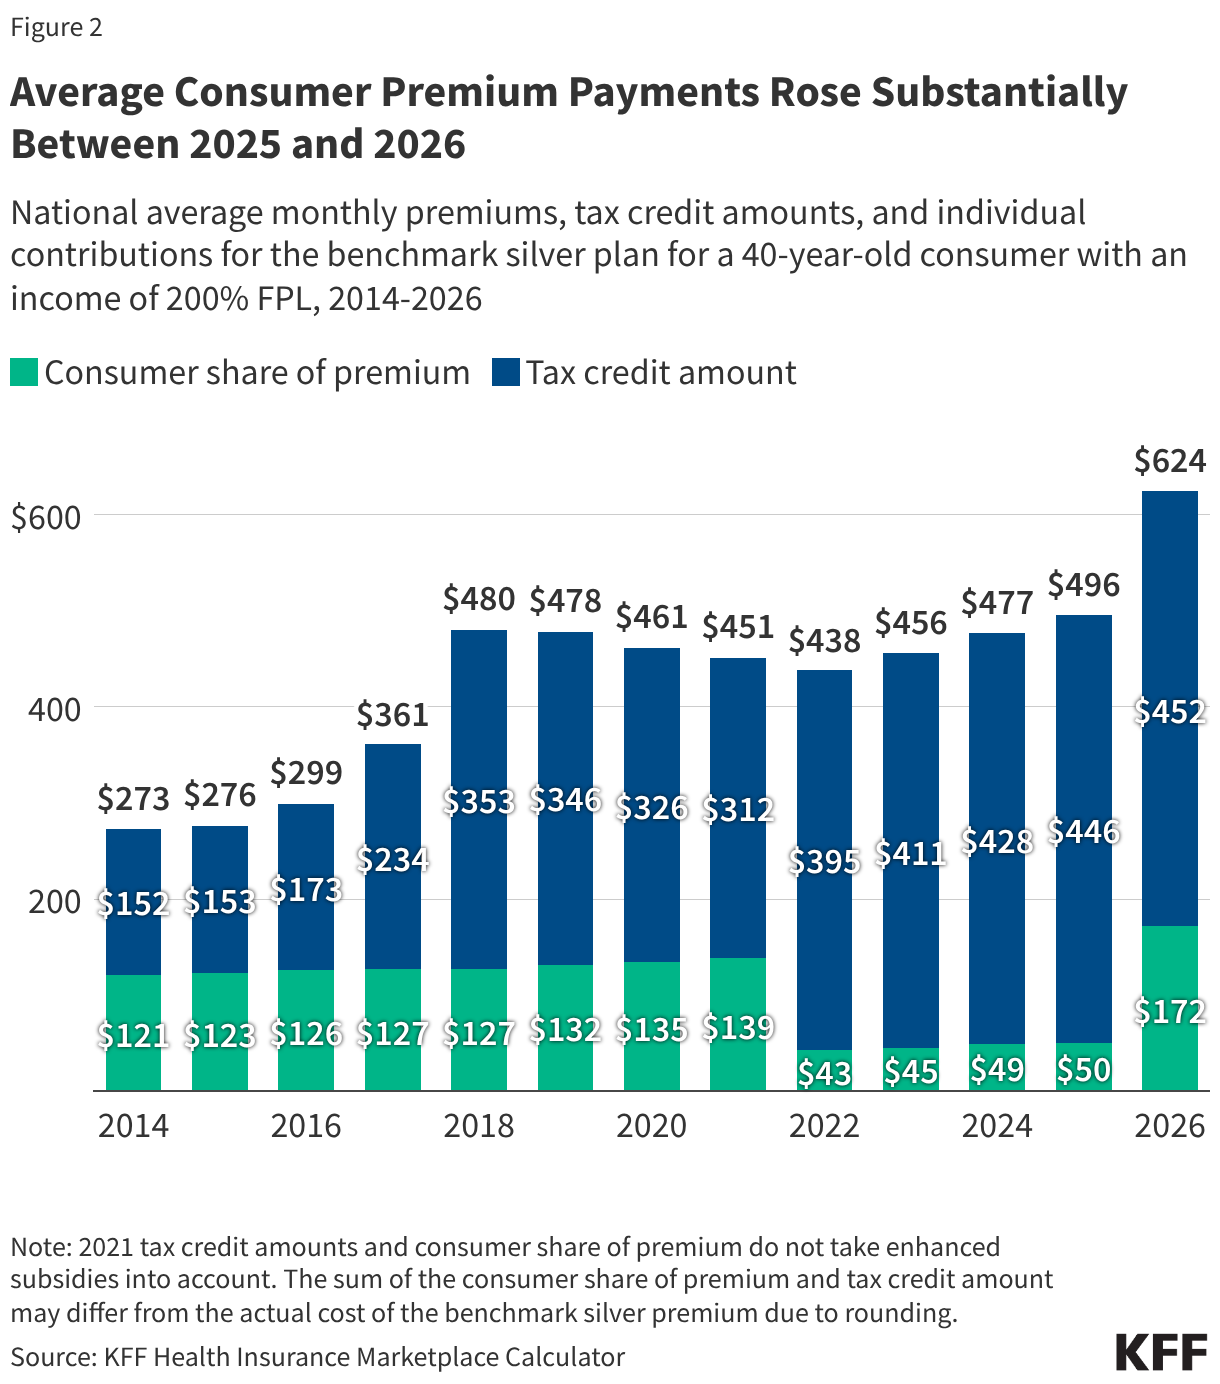
Average Consumer Premium Payments Rose Substantially Between 2025 and 2026 (Stacked column chart)

Effectuated enrollment declined in nearly every state from 2025 to 2026, though the size of the decline varied substantially. New Mexico was the only state to see an increase in effectuated enrollment, growing 14% between 2025 and 2026, coinciding with the state's premium assistance program that fully replaced the expiring federal enhanced tax credits with state-funded subsidies. Effectuated enrollment in Illinois, Connecticut, Pennsylvania, Idaho, the District of Columbia, Massachusetts, and Texas held relatively flat or fell by less than 5%. Of these states, Texas is the only state that is not a state-based Marketplace. Enrollment in Texas may have been buoyed by a state rule that mandates substantial silver loading, which can lead to more subsidized people being eligible for a bronze plan, or in some cases a gold plan, with little or no premium payment.

At the other end of the spectrum, effectuated enrollment fell by just over 32% in Ohio and Oklahoma, and by more than a quarter in Arizona (30%), South Carolina (29%), Indiana (28%), Michigan (27%), Minnesota (27%), Mississippi (26%), and Louisiana (26%). Of these states, Minnesota is unlike the others in that it offers a Basic Health Program covering low-income people who would otherwise sign up on-exchange. With a relatively higher-income group of Marketplace enrollees, Minnesota enrollees may have been disproportionately affected by the return of the subsidy cliff as enhanced tax credits expired.

A sortable table in the appendix shows the change in enrollment for each state, alongside other information about the type of Marketplace, whether state subsidies are available, and the effectuation rate.

Figure 3

States that run their own enrollment platforms, and particularly those that offered state-funded subsidies, generally saw a smaller drop in enrollment (or an increase, in the case of New Mexico). When weighted by enrollment in each state, those that use the HealthCare.gov platform (and do not offer state-specific subsidies) saw a decline in effectuated enrollment of 15% from 2025 to 2026. However, state-based Marketplaces experienced a 6% decline during the same period. States that offered state-funded subsidies all saw below-average declines in enrollment, or an increase in the case of New Mexico. 

Figure 4

Of the 26 states with effectuated enrollment drops smaller than the national average, 18 were state-based Marketplaces, including all nine that offered their own state-funded subsidies. These differences across states suggest that the availability of state-level premium assistance helped cushion the effect of expiring enhanced premium tax credits on enrollees' ability to maintain coverage, though enrollment changes likely also reflect broader differences in state populations and Marketplace administration.

Figure 5

Changes in both plan selections and effectuated enrollment from 2025 to 2026 varied considerably among states. However, changes in effectuated enrollment were not always well predicted by earlier reported changes in plan selections. In most states (37), both plan selections and effectuated enrollment declined, and the gap between the two widened, meaning that drops in plan selections underpredicted the change in effectuated enrollment. This pattern was particularly pronounced in states such as South Carolina, where plan selections fell 7% but effectuated enrollment fell 29%; Michigan, where plan selections fell 6% but effectuated enrollment fell 27%; and Minnesota, where plan selections fell 8% but effectuated enrollment fell 28%.

For nine states, plan selections rose from 2025 to 2026 but effectuated enrollment fell, reflecting a declining effectuation rate. Louisiana saw the largest divergence: plan selections increased by about 1% but effectuated enrollment fell by 27%. Texas showed the largest difference by number of enrollees: about 206,000 more people signed up this year (a 5% increase in sign-ups), with effectuated enrollment ultimately falling by about 146,000 people (a 4% decrease). Connecticut, Idaho, Massachusetts, Maryland, Pennsylvania, and Rhode Island saw smaller versions of this trend, with modest increases in plan selections alongside slight declines in effectuated enrollment.
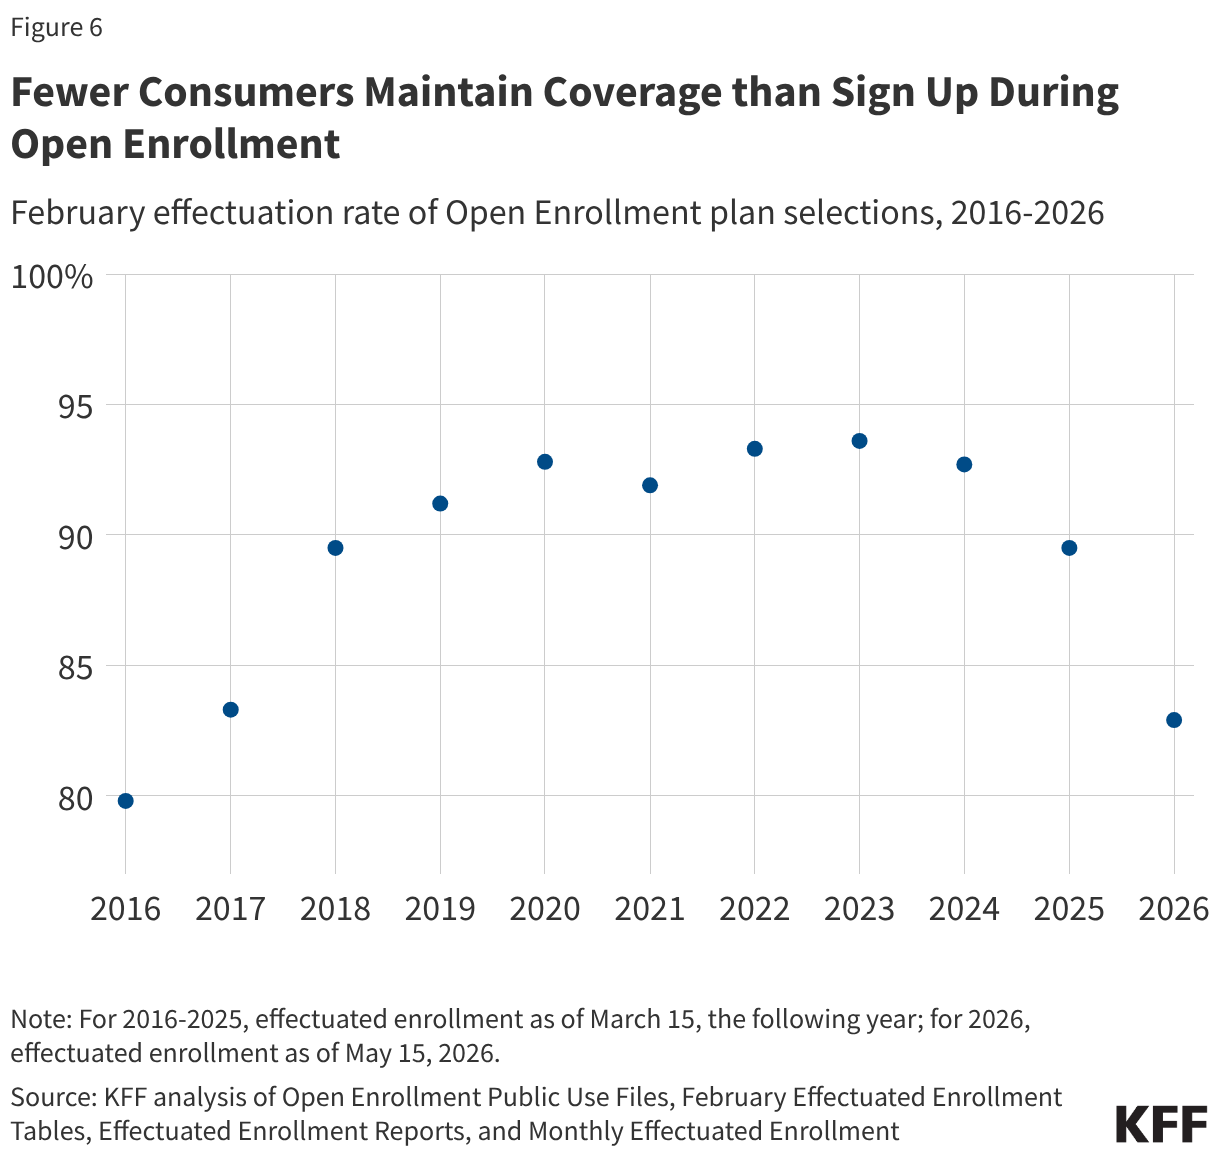
Fewer Consumers Maintain Coverage than Sign Up During Open Enrollment (Line chart)

Nationwide, the February effectuation rate fell from 90% in 2025 to 83% in 2026. This means a larger share of the people who signed up for coverage during open enrollment did not maintain their coverage, perhaps because they did not pay the first month's premium, canceled after enrolling, or fell behind on payments and had their coverage terminated. Since 2019, the effectuation rate (measured past the end of the three-month grace period for February premium payment) has been above 90% but was lower in the early years of Marketplace coverage.

This year, Mississippi had the lowest effectuation rate (61%), meaning nearly two in five consumers who signed up during open enrollment did not maintain coverage past January. Similarly, South Carolina, Louisiana, Indiana, and Oklahoma also saw effectuation rates below 70% in 2026. By contrast, New Mexico, California, Nevada, Vermont, and Idaho each had effectuation rates of 95% or more.

Figure 7

States that run their own Marketplaces generally maintained higher effectuation rates than states that use HealthCare.gov. The ten states with the lowest effectuation rates all use the Healthcare.gov platform, while the ten states with the highest effectuation rates are all state-based Marketplaces. These differences may reflect variation in state populations, subsidy structures, or outreach and enrollment assistance efforts. Of state-based Marketplaces, Minnesota and the District of Columbia were the only ones to see lower-than-average effectuation rates. Both markets skew relatively higher-income, as both offer Basic Health Programs that cover lower-income enrollees who would otherwise sign up on exchange. 

Figure 8

As with smaller drops in effectuated enrollment, states that implemented state-based subsidy programs to help offset the expiration of the enhanced premium tax credits through their state-based Marketplaces saw higher effectuation rates. Of the nine states offering state-based premium subsidies, seven saw effectuation rates higher than 90%, and all saw effectuation rates higher than the U.S. average. New Mexico, which, as mentioned earlier, fully replaced the lost enhanced premium tax credits through state funds, had the highest effectuation rate among all states at 96%.

These patterns suggest that state policies designed to blunt the effect of rising premiums may be associated with higher rates of enrollees maintaining active coverage, though other factors—such as income levels, Marketplace type, and state outreach efforts—likely also play a role. All states that offered state subsidies to backfill some portion of the expired enhanced premium tax credits were above the median change in effectuated enrollment.

Appendix

Plan Selections and Effectuated Enrollment (Table)

Methods

Open enrollment plan selections and monthly effectuated enrollment were collected from Centers for Medicare & Medicaid Services (CMS) sites. Effectuated enrollment in this current analysis refers to enrollees with any coverage in February. For 2025, effectuated enrollment is as of March 15, 2026; for 2026, as of May 5, 2026. Both of these dates are past end of the February premium payment grace period for consumers who had effectuated coverage. State-based subsidy information was obtained from state government websites; see Figure 3 for links to source data. States that operate their own exchanges but use the HealthCare.gov platform are included in the HealthCare.gov category; none of them provide state-funded premium assistance. Weighted average enrollment changes by platform type were calculated using the above described categorizations. Illinois, which switched from using HealthCare.gov in 2025 to its own state-based Marketplace platform in 2026, is counted as a state-based Marketplace for change in effectuated enrollment.

An analysis by ASPE reported the 2025 February effectuated enrollment total to be 22.1 million, but the CMS monthly effectuated enrollment data report a total of 21.8 million enrollees in February 2025. Effectuated enrollment totals may differ across data sources, potentially due to the date of measurement. This KFF analysis is based on CMS monthly effectuated enrollment data (linked above) which indicated a total of 21.8 million effectuated enrollees.