Abortion in the United States Dashboard

On June 24, 2022, the Supreme Court overturned Roe v. Wade, eliminating the federal constitutional standard that had protected the right to abortion. Without any federal standard regarding abortion access, states will set their own policies to ban or protect abortion. The Abortion in the United States Dashboard is an ongoing research project tracking state abortion policies and litigation following the overturning of Roe v. Wade.

Click on the buttons or scroll down to see all the content. It will be updated as new information is available.

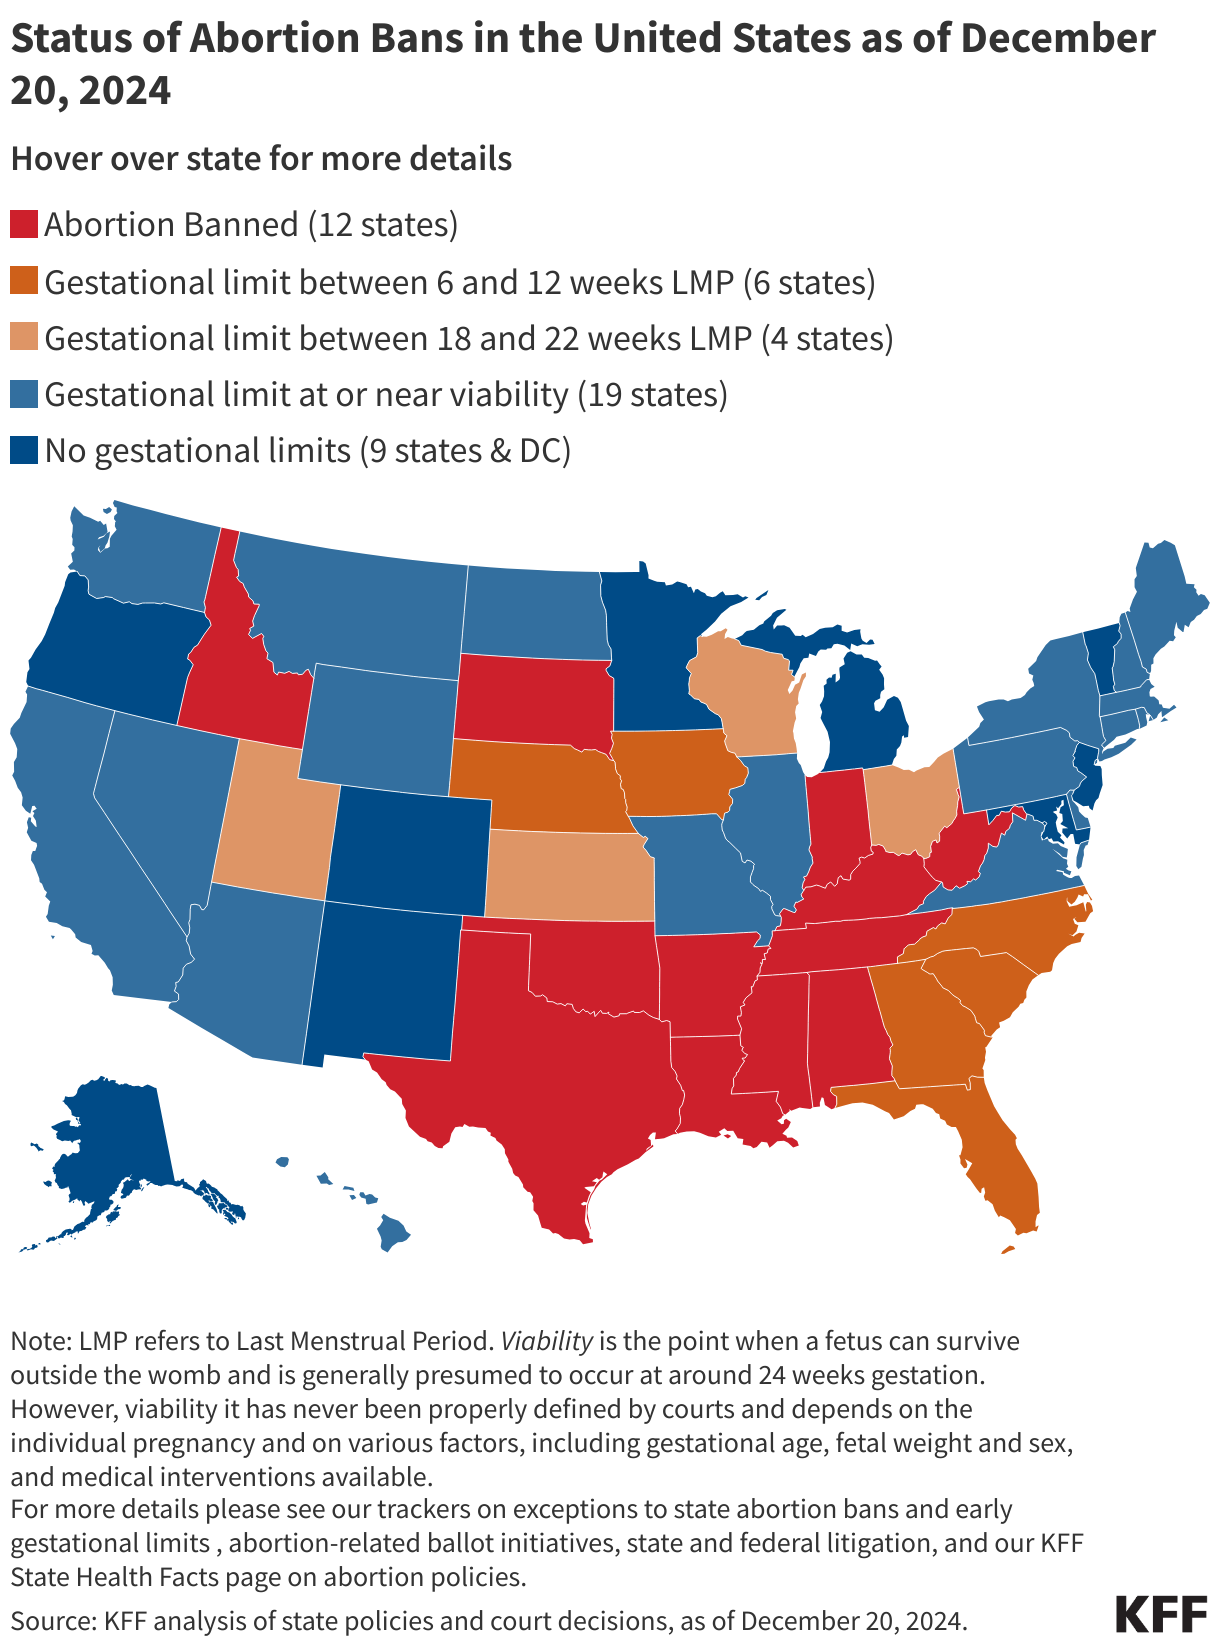
Map of the United States showing the status of abortion bans as of March 9, 2026. 

Abortion banned in 13 states: Alabama, Arkansas, Idaho, Indiana, Kentucky, Louisiana, Mississippi, North Dakota, Oklahoma, South Dakota, Tennessee, Texas, West Virginia

Gestational limit between 6 and 12 weeks LMP in effect in 7 states: Florida (6 weeks), Georgia (6 weeks), Iowa (6 weeks), Nebraska (12 weeks), North Carolina (12 weeks), South Carolina (6 weeks), Wyoming (6 weeks).

Gestational limit between 15 and 22 weeks LMP in effect in 4 states: Kansas, Ohio, Utah and Wisconsin

Gestational limits at or near viability in 18 states: Arizona, California, Connecticut, Delaware, Hawaii, Illinois, Maine, Massachusetts, Missouri, Montana, Nevada, New Hampshire, New York, Pennsylvania, Rhode Island, Virginia, Washington

No gestational limits in 9 states and DC: Alaska, Colorado, DC, Maryland, Michigan, Minnesota, New Jersey, New Mexico, Oregon, Vermont

NEW RELEASES

The Legal and Policy Landscape of Crisis Pregnancy Centers 

Women's Health Policy

This brief examines the legal status of Crisis Pregnancy Centers, attempts to regulate them, and future efforts to expand their footprints as they gain more recognition and funding from local, state, and federal programs.

BALLOT MEASURES

KEY FACTS

Over four in ten (45%) abortions occur by six weeks of gestation, 36% are between seven and nine weeks, and 13% at 10-13 weeks. Just 7% of abortions occur after the first trimester.

The Vast Majority of Abortions in 2022 Occurred Prior to 10 Weeks of Gestation

MEDICATION Abortion


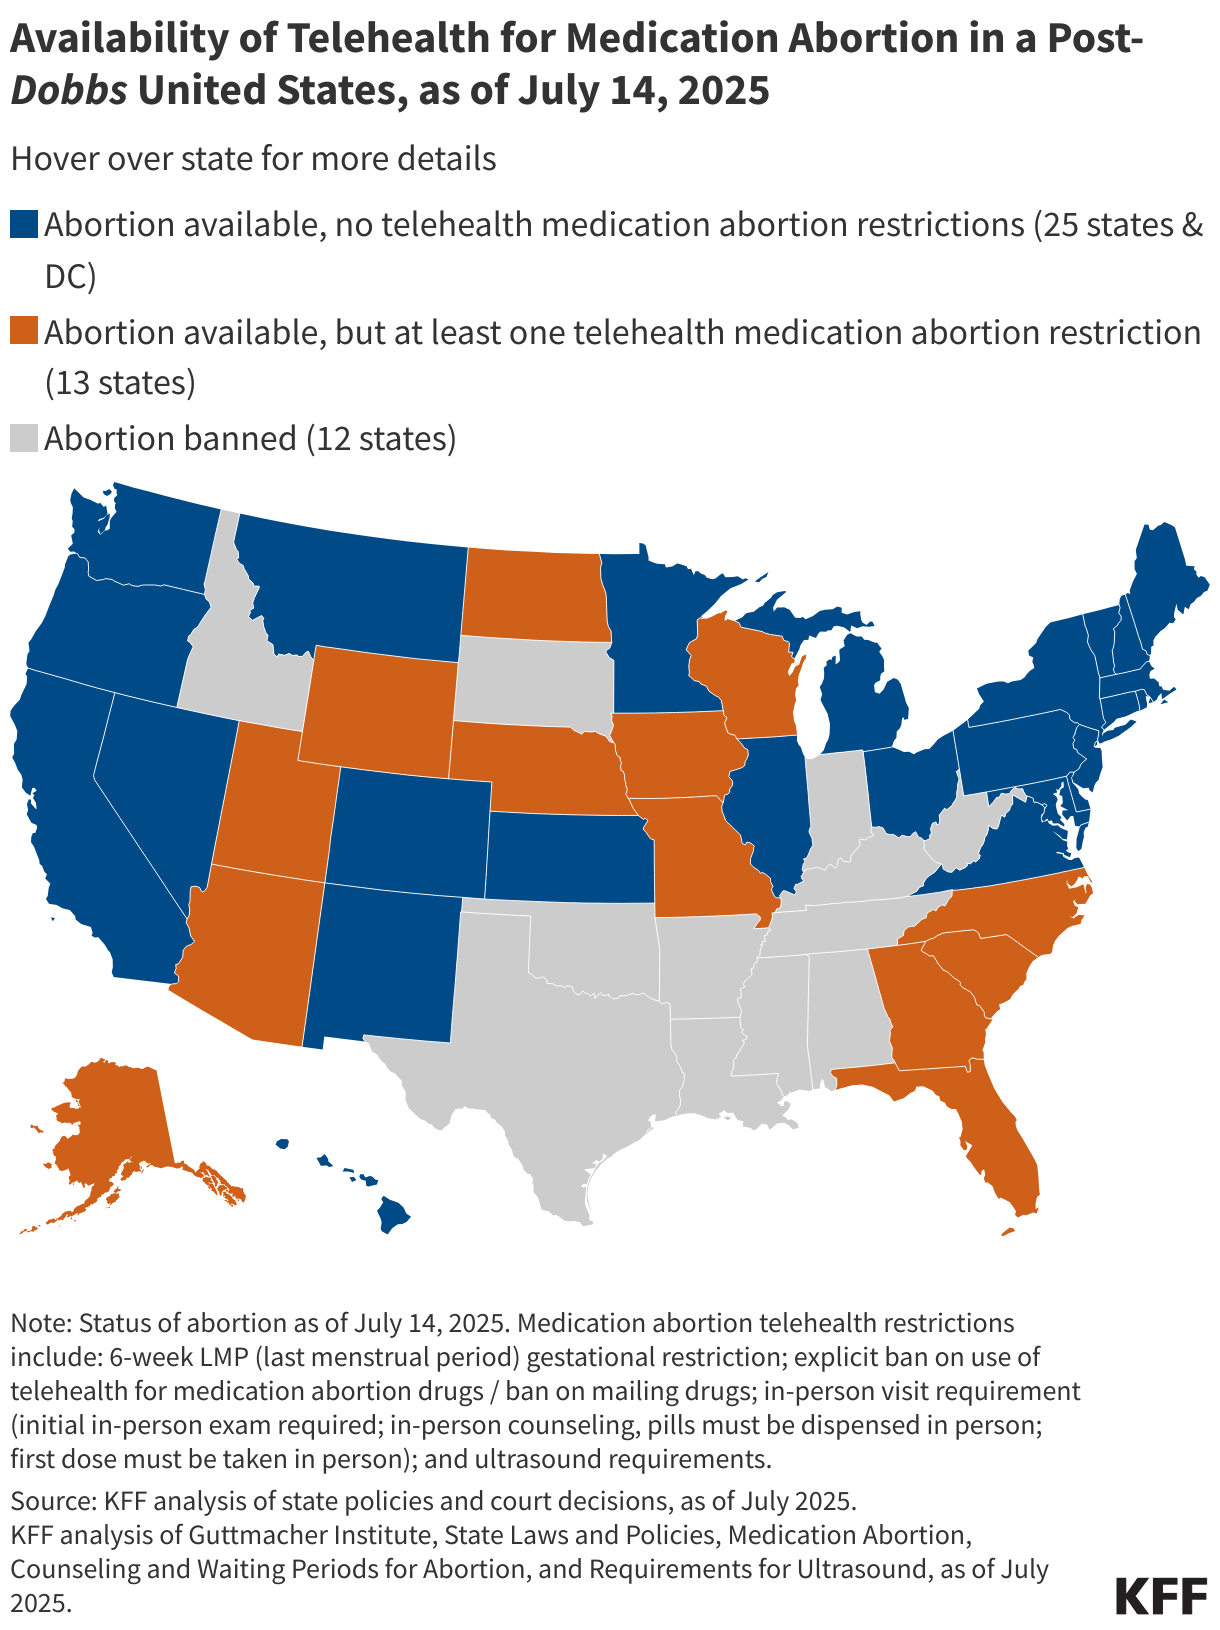
Availability of Telehealth for Medication Abortion in a Post-Dobbs United States, as of May 14, 2026 (Choropleth map)

The Intersection of State and Federal Policies on Access to Medication Abortion Via Telehealth after Dobbs

This brief reviews current state and federal policies, ongoing litigation, and potential federal actions that may impact access to telehealth for medication abortion.

COVERAGE

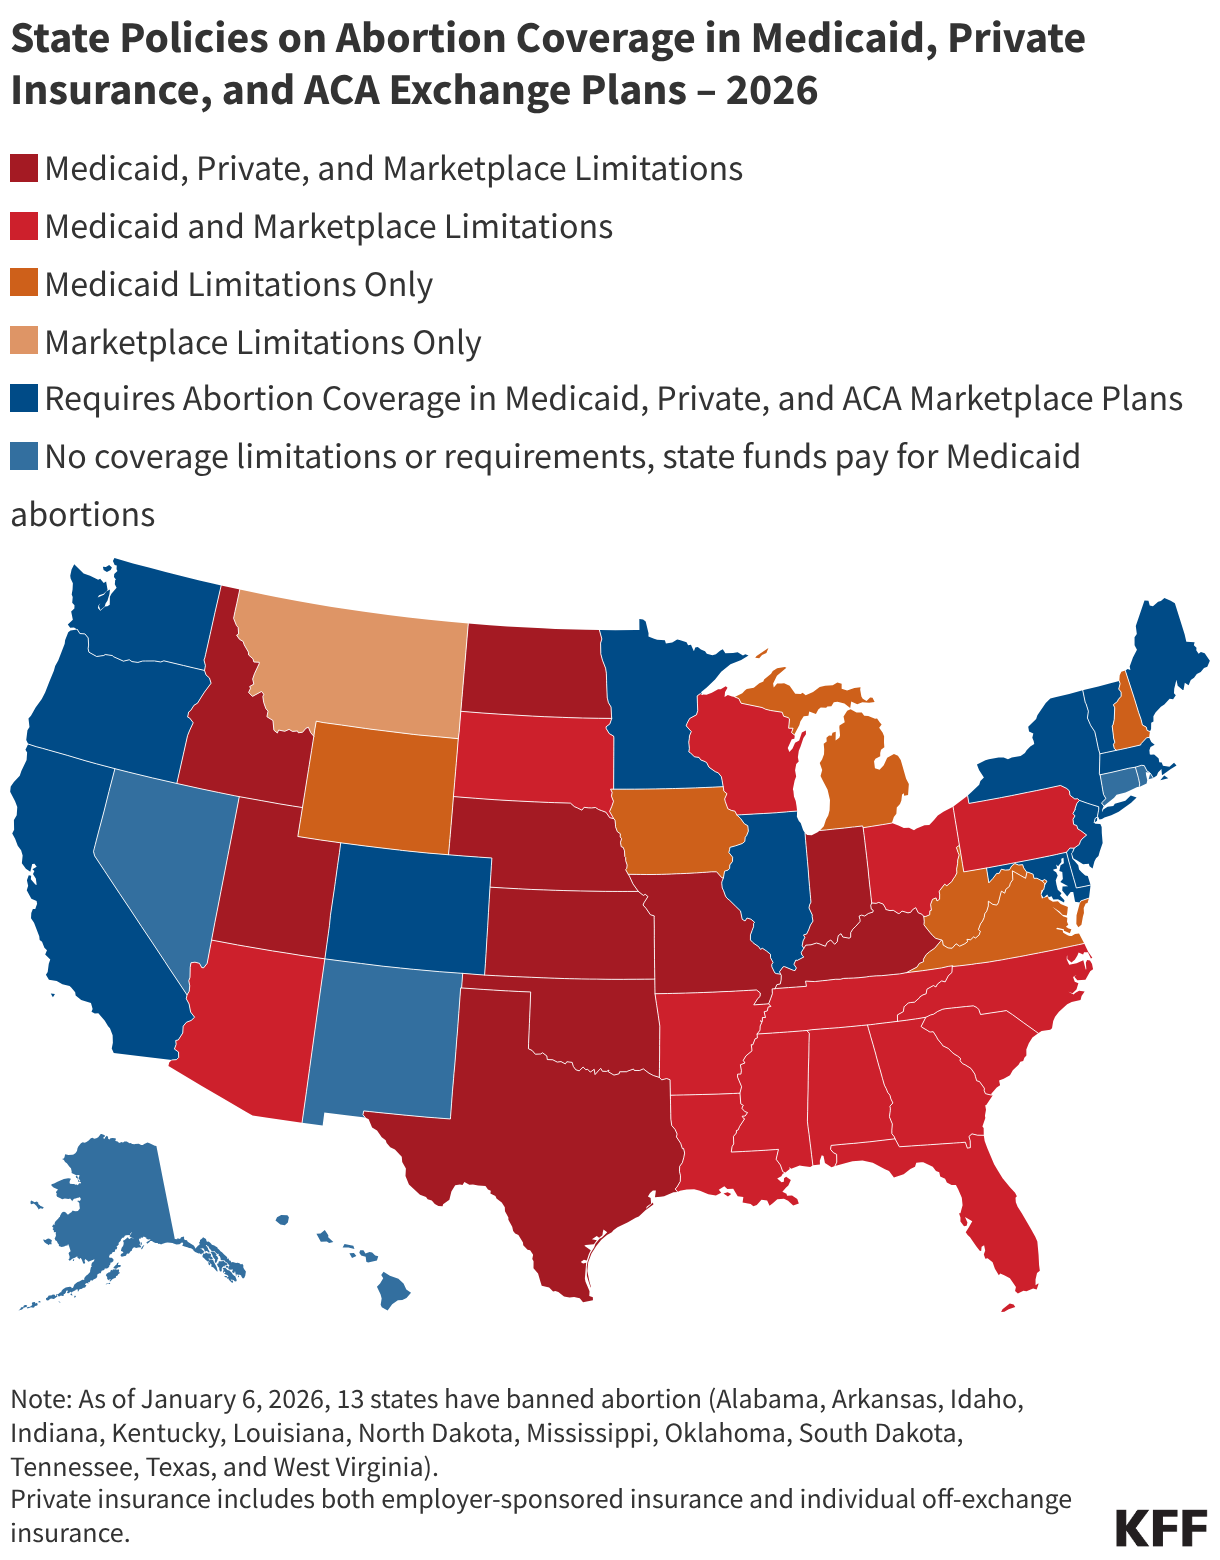
State Policies on Abortion Coverage for Medicaid, Private Insurance, and ACA Exchange Plan Enrollees – 2026 (Choropleth map)

How State Policies Shape Access to Abortion Coverage

Several states have enacted private plan restrictions and have also banned abortion coverage from ACA Marketplace plans. Currently, there are 10 states that restrict abortion coverage in private plans and 25 that ban coverage in any Marketplace plans.

Abortion Decision Renews Questions About Employer Access to Health Information

This Policy Watch takes a look at employers ability to access abortion information when their health plan covers abortion services. With some states criminalizing entities who assist in abortions, employers and providers face legal jeopardy and existing privacy laws such as HIPAA (the Health Insurance Portability and Accountability Act) may be limited in their privacy protections.


Employer Coverage of Travel Costs for Out-of-State Abortion

This Policy Watch gives an overview of employers offering to cover travel expenses for workers who need to go out of state for an abortion in the context of increasing restrictions on abortion around the country. We discuss who is offering these benefits, the implications for workers, and some of the legal and political concerns for employers.

Coverage of Abortion in Large Employer-Sponsored Plans in 2023

This brief presents findings from the 2023 KFF Employer Health Benefits Survey on coverage of abortion services in large employer-sponsored health plans, changes employers made to abortion coverage since the 2022 Supreme Court ruling, and employers’ provision of financial assistance for travel out of state to obtain an abortion.

RACIAL & ETHNIC DISPARITIES

Polling

KFF Health Tracking Poll: Mifepristone and the Midterms

Amid an ongoing FDA re-review of mifepristone, awareness of the safety and prevalence of the abortion pill remains limited. This KFF poll also finds that the voters who say abortion policy is an important issue for 2026 midterm candidates to discuss are disproportionately Democrats.

KFF Health Tracking Poll: Knowledge and Views of Medication Abortion

This KFF Health Tracking Poll finds that many, including women of reproductive age, remain unfamiliar with key facts about mifepristone. Fewer than half of all adults say they believe abortion pills are safe now, compared to over half of all adults two years ago. This poll explores awareness and perception of the recent FDA review of the medication, and support for policies aimed at restricting it.


Abortion Experiences, Knowledge, and Attitudes Among Women in the U.S.

This brief provides new information from the 2024 KFF Women’s Health Survey about women’s experiences with abortion, the fallout of overturning Roe v. Wade, women’s knowledge about abortion laws in their states including medication abortion, as well as their opinions on the legality of abortion.

Women and Abortion in Florida

This brief provides information about abortion experiences, awareness, and attitudes of Florida women ages 18 to 49, based on findings from the 2024 KFF Women’s Health Survey, a nationally representative survey on health care issues.

Women and Abortion in Arizona

This brief provides information about abortion experiences, awareness, and attitudes of Arizona women ages 18 to 49, based on findings from the 2024 KFF Women’s Health Survey, a nationally representative survey on health care issues.

STATE PROFILES FOR WOMEN'S HEALTH

Abortion Policies by State

State gestational limits, waiting periods & ultrasound requirements, insurance coverage and medication abortion restrictions

Variability in Reimbursement Rates for State-funded Abortion Services for Medicaid Enrollees: A 2026 Update

Authors: Brittni Frederiksen, Olivia Podber, and Alina Salganicoff
Published: Aug 7, 2026
  • Among states that use state-appropriated funds to pay for abortion for Medicaid enrollees, variability in abortion payment rates for the same procedures is considerable. Twenty-one states currently use their own funds to cover abortion services for Medicaid enrollees beyond the limits imposed by the federal Hyde Amendment, which bans federal funding of abortions in cases other than pregnancies that result from rape, incest, or are a life threat. In these states, Medicaid medication abortion rates range from $162 (RI) to $869 (WA) (median $597); dilation and curettage (D&C) procedure rates go from $126 (RI) to a high of $1,000 (NY) (median $378); and dilation and evacuation (D&E) procedure rates vary from $126 (RI) to $1,920 (IL) (median $636).  
  • Only a few states significantly increased their state-funded reimbursement rates for abortion services for Medicaid enrollees in the past two years. Most states that cover abortions for their enrollees have not changed or only modestly increased their reimbursement rates. Among the states that increased D&C rates, only 5 did so at or above the rate of health care inflation. Similarly, among states that increased D&E reimbursement rates, only 6 increased rates at or above the rate of health care inflation over the past two years. Over half (57%, 12 states) have not increased D&C procedure reimbursement rates, and 52% (11 states) have not increased D&E procedure reimbursement rates. 
  • Despite the increased complexity of abortion procedures later in pregnancy, Medicaid reimbursement rates are not substantially higher than rates for earlier-stage procedures in most states. Reimbursement rates for abortions later in pregnancy typically do not reflect the increased complexity and costs associated with later-stage care. The median reimbursement rate for states that fund abortions for Medicaid enrollees was $378 for D&C—typically used earlier in pregnancy—vs. $636 for D&E, which is generally used for abortion procedures performed later in pregnancy. These rates are considerably lower than previously published research on self-pay abortion charges for the same procedures.

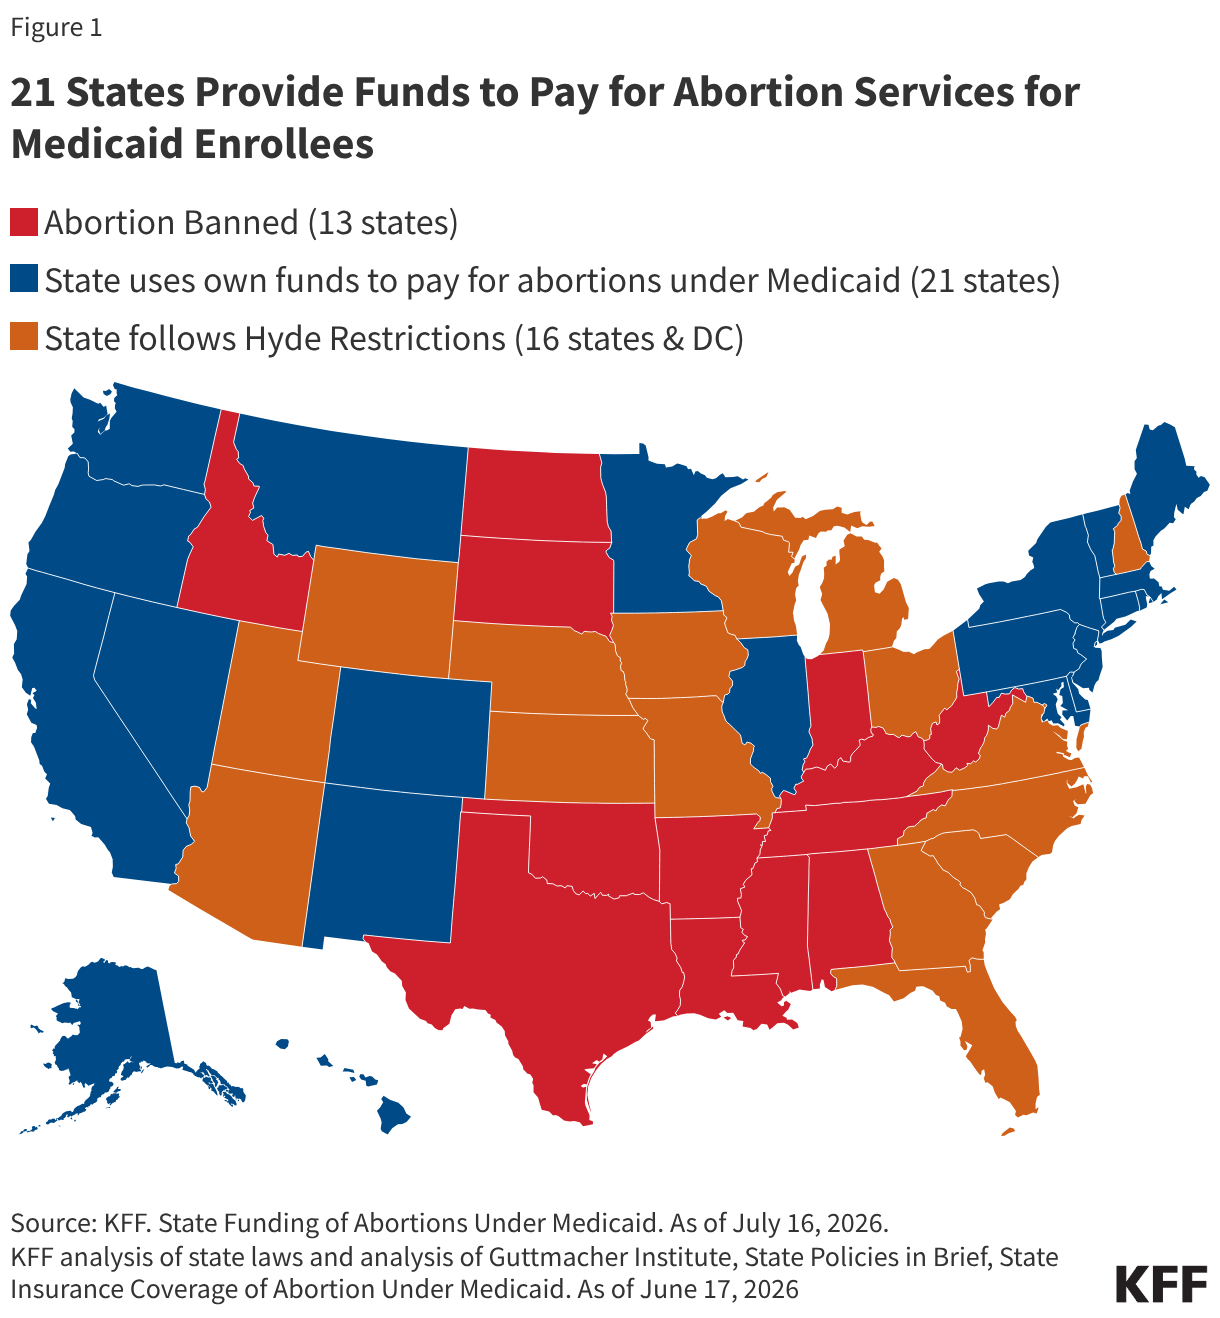
Since the Dobbs decision in 2022 overturning Roe v. Wade, 13 states have banned the provision of abortion with few exceptions. In the remaining states where abortion is legal, another barrier to abortion services has been the federal Hyde Amendment, which prohibits the use of federal Medicaid funds for abortion with limited exceptions for pregnancies that endanger the life of the pregnant person, or that result from rape or incest. States may use their own revenues to pay for abortion services for Medicaid enrollees beyond the federal financing restrictions, and 21 currently use their own state funds to pay for abortions for Medicaid enrollees, while 16 states & DC where abortion provision is not banned follow the Hyde Amendment restrictions (Figure 1). Medicaid reimbursement rates are established by the states under broad federal guidelines and have historically been lower than those paid by Medicare and are even lower relative to private insurance rates.

In the case of Medicaid, lower reimbursement rates can lead to abortion providers experiencing financial shortfalls, challenging their long-term sustainability and ability to serve Medicaid enrollees. Lower reimbursement rates have been linked to higher out-of-pocket costs for Medicaid beneficiaries, who are overwhelming low-income, further constraining their access to abortion care. 

To understand the status of Medicaid payment for abortion services four years post-Dobbs, KFF researchers reviewed Medicaid physician fee schedules for medication and procedural abortions in states that do not ban abortion, updating an analysis first published in 2024. This analysis focuses on states where abortion provision is not banned, including those using state funds to pay for abortions for Medicaid enrollees as well those that only cover abortions under Hyde exceptions, and it excludes the 13 states where abortion provision is banned. 

Figure 1 is a map of the United States titled, “21 States Provide Funds to Pay for Abortion Services for Medicaid Enrollees.” States are color-coded into three categories: blue indicates states that use their own funds to pay for abortions under Medicaid (21 states), orange indicates states that follow the federal Hyde Amendment restrictions (16 states and Washington, DC), and red indicates states where abortion is banned (13 states). States that use their own state funds to pay for abortions under Medicaid (blue states) are concentrated on the West Coast, the Northeast, and parts of the Midwest and Southwest. States where abortion is banned (red states) are concentrated across the South and parts of the Great Plains. States that follow the federal Hyde Amendment restrictions, but do not ban abortion (orange states) are primarily located in the Mountain West, Midwest, and Southeast. The map includes data current as of July 16, 2026.

How Abortion Payment Rates Are Structured

Medicaid services are financed via two pathways: fee-for-service (FFS) and managed care arrangements. The reimbursement rates presented in this brief are for FFS claims, as contracted managed care rates are not typically publicly available. The FFS reimbursement rates reported in this brief are for non-facility (e.g., outpatient clinics or physician offices), provider-only rates (e.g., excluding any facility rates), since most abortions are performed outside of a hospital setting. States such as Connecticut, Massachusetts, Nevada, and Washington use different reimbursement fee schedules for family planning and abortion clinics. These reimbursement rates are often higher than physician fee schedules. This analysis uses the family planning and abortion clinic rates, when available.

State Medicaid programs also differ in the payment structures they use for abortion services. Some states use a bundled reimbursement structure for abortion services, where ancillary services provided alongside the abortion are included in the bundled payment rate. Other states use unbundled billing, and providers can bill separately for all services provided with the abortion. Additional services often billed for on the day of the abortion in states that use unbundled codes may include an ultrasound, administered medication, a nerve block, and Rh testing, which are outlined in coding guides developed by the Reproductive Health Access Project for manual vacuum aspiration abortion and medication abortion. Median reimbursement rates for each of these services from state Medicaid physician fee schedules are reported in the tables throughout this brief.

Even when Medicaid reimburses for abortion services, providers have reported that Medicaid reimbursement rates are substantially lower than what they receive from self-pay patients. Because there are limited and outdated data on the actual cost of providing abortion care, self-pay prices can serve as a useful proxy for provider costs, although they may underestimate true costs if they reflect discounts provided to patients by abortion funds. Research conducted before the Dobbs decision illustrates the breadth of this reimbursement gap. A 2020 study reviewed 2017 Medicaid and Medicare physician fees schedules for D&C and D&E procedures across 45 states and D.C. and found that median Medicaid reimbursement rates for first- and second-trimester abortions covered only 37% and 41% of the amount charged to self-pay patients for the procedures, respectively. The study did not address reimbursement rates for abortions after the second trimester. Providers also reported instances in which they received no reimbursement for abortions that were eligible for Medicaid coverage under the Hyde Amendment. The study's authors concluded that this reimbursement gap, particularly when combined with inconsistent reimbursement practices, may further discourage providers from participating in Medicaid.

More recent data on self-pay prices support these findings. A 2024 report on self-pay charges for abortion services from 2017 to 2023 found median charges of $563 for medication abortion, $650 for a first-trimester procedural abortion (D&C), and $1,000 for a second-trimester abortion (D&E). These quoted self-pay prices are substantially higher than Medicaid reimbursement rates in many states, reinforcing that a gap exists between what providers typically charge and what Medicaid pays. 

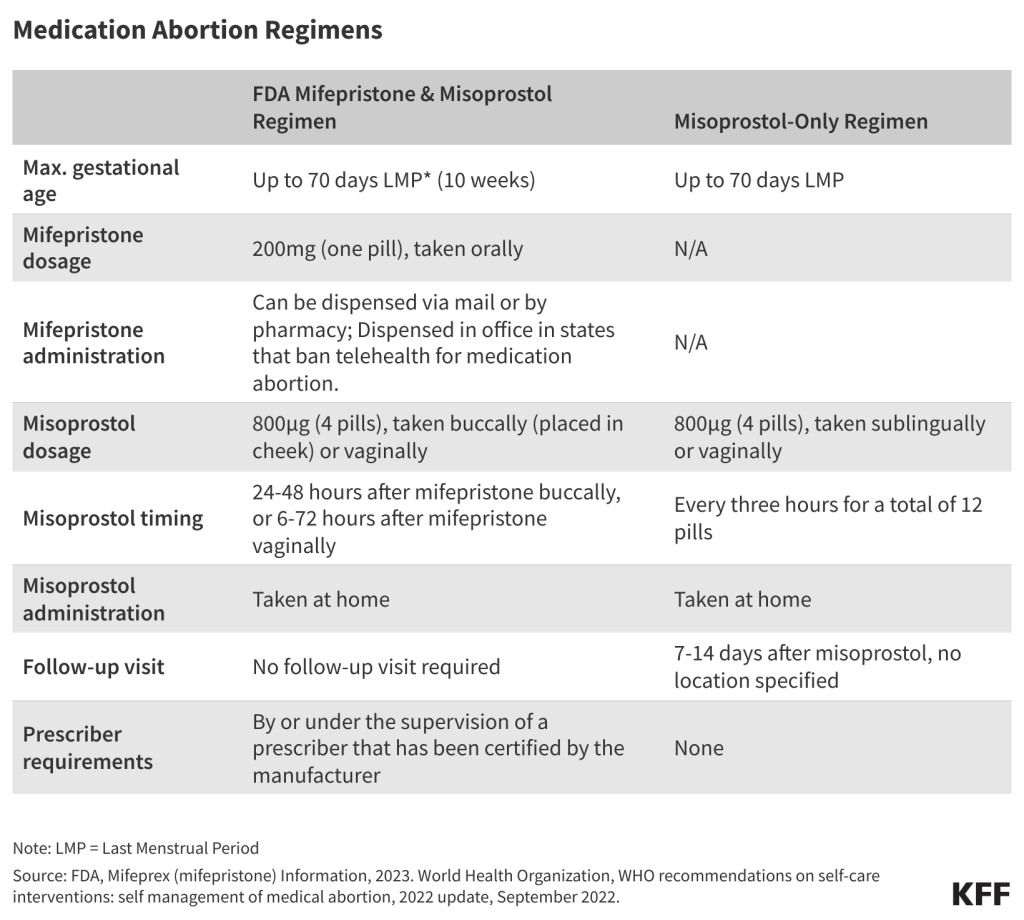
In 2023, medication abortion, a two-drug regimen using mifepristone and misoprostol that is FDA-approved to terminate pregnancies up to 10 weeks in the U.S., accounted for 65% of all abortions. This share has increased since the FDA removed the in-person dispensing requirements in 2021, making medication abortion via telehealth, mail, and pharmacies more accessible. 

Medication abortion can be billed using three separate procedure codes, and often all three codes are billed at the same time. There are codes for two pharmaceuticals—mifepristone (HCPCS S0190) and misoprostol (HCPCS S0191)—as well as a global medication abortion code (HCPCS S0199) that includes all affiliated services and supplies (e.g., patient counseling, office visits, confirmation of pregnancy by HCG, ultrasound to confirm duration of pregnancy, ultrasound to confirm completion of abortion). 

States typically take two approaches to reimburse for medication abortion services: (1) a bundled payment using the global medication abortion code plus the medications (billed either through medical services or pharmacy billing channels); or (2) payment for separate services, like office visits and ultrasounds, plus the medications. 

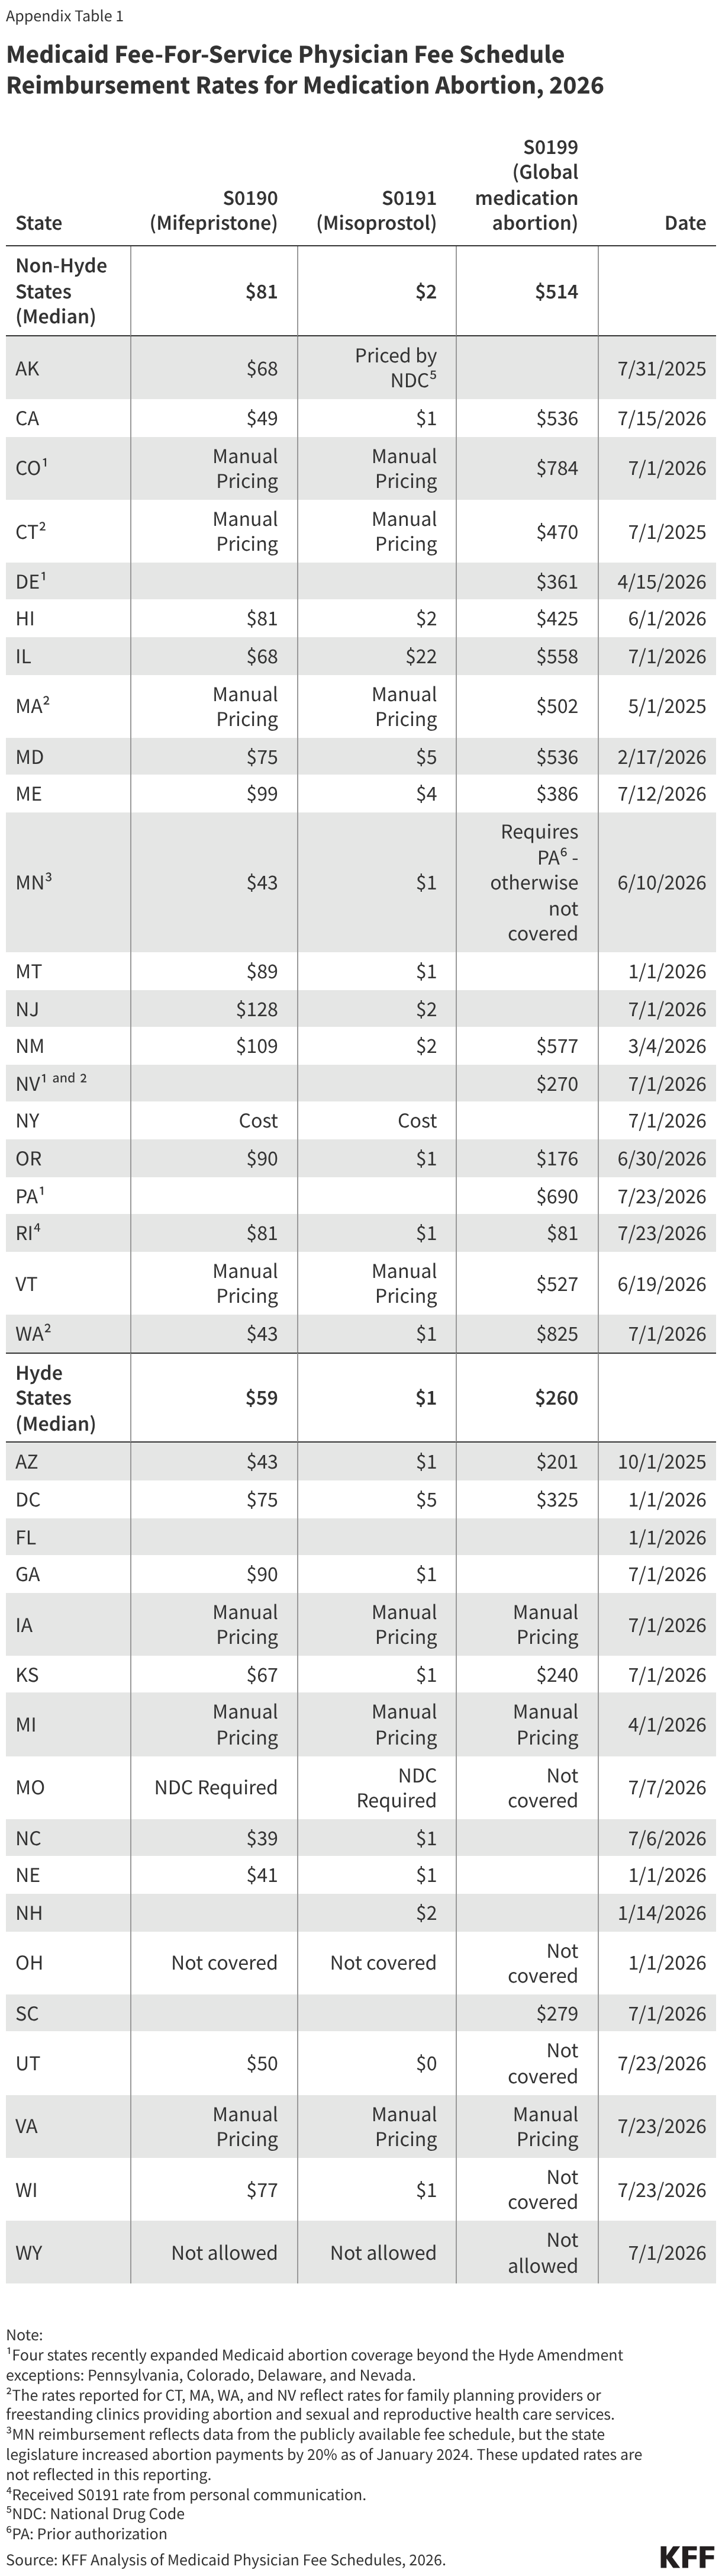
Twenty out of 21 states that use state funds to pay for abortion services for Medicaid enrollees list reimbursement rates for at least one of the three medication abortion codes, with 16 listing rates for the global medication abortion code, 13 listing rates for mifepristone, and 12 listing rates for misoprostol. The one state not accounted for is New York; while they do not reimburse for the global medication code, on their publicly available fee schedule they reimburse at the “cost” of the drugs to abortion providers for both mifepristone and misoprostol. The median Medicaid reimbursement rate for the global medication abortion code is $514, ranging from a low of $81 in Rhode Island to a high of $825 in Washington (Figure 2). The median reimbursement rate for mifepristone is $81, ranging from a low of $43 in Washington to a high of $128 in New Jersey. The median reimbursement rate for misoprostol is $2, which ranges from less than $1 in Washington to $22 in Illinois. When the median amounts for all three medication abortion codes are summed together, the median reimbursement rate for medication abortion is $597. However, the range of summed codes across states is quite large, from $162 in Rhode Island to $869 in Washington.
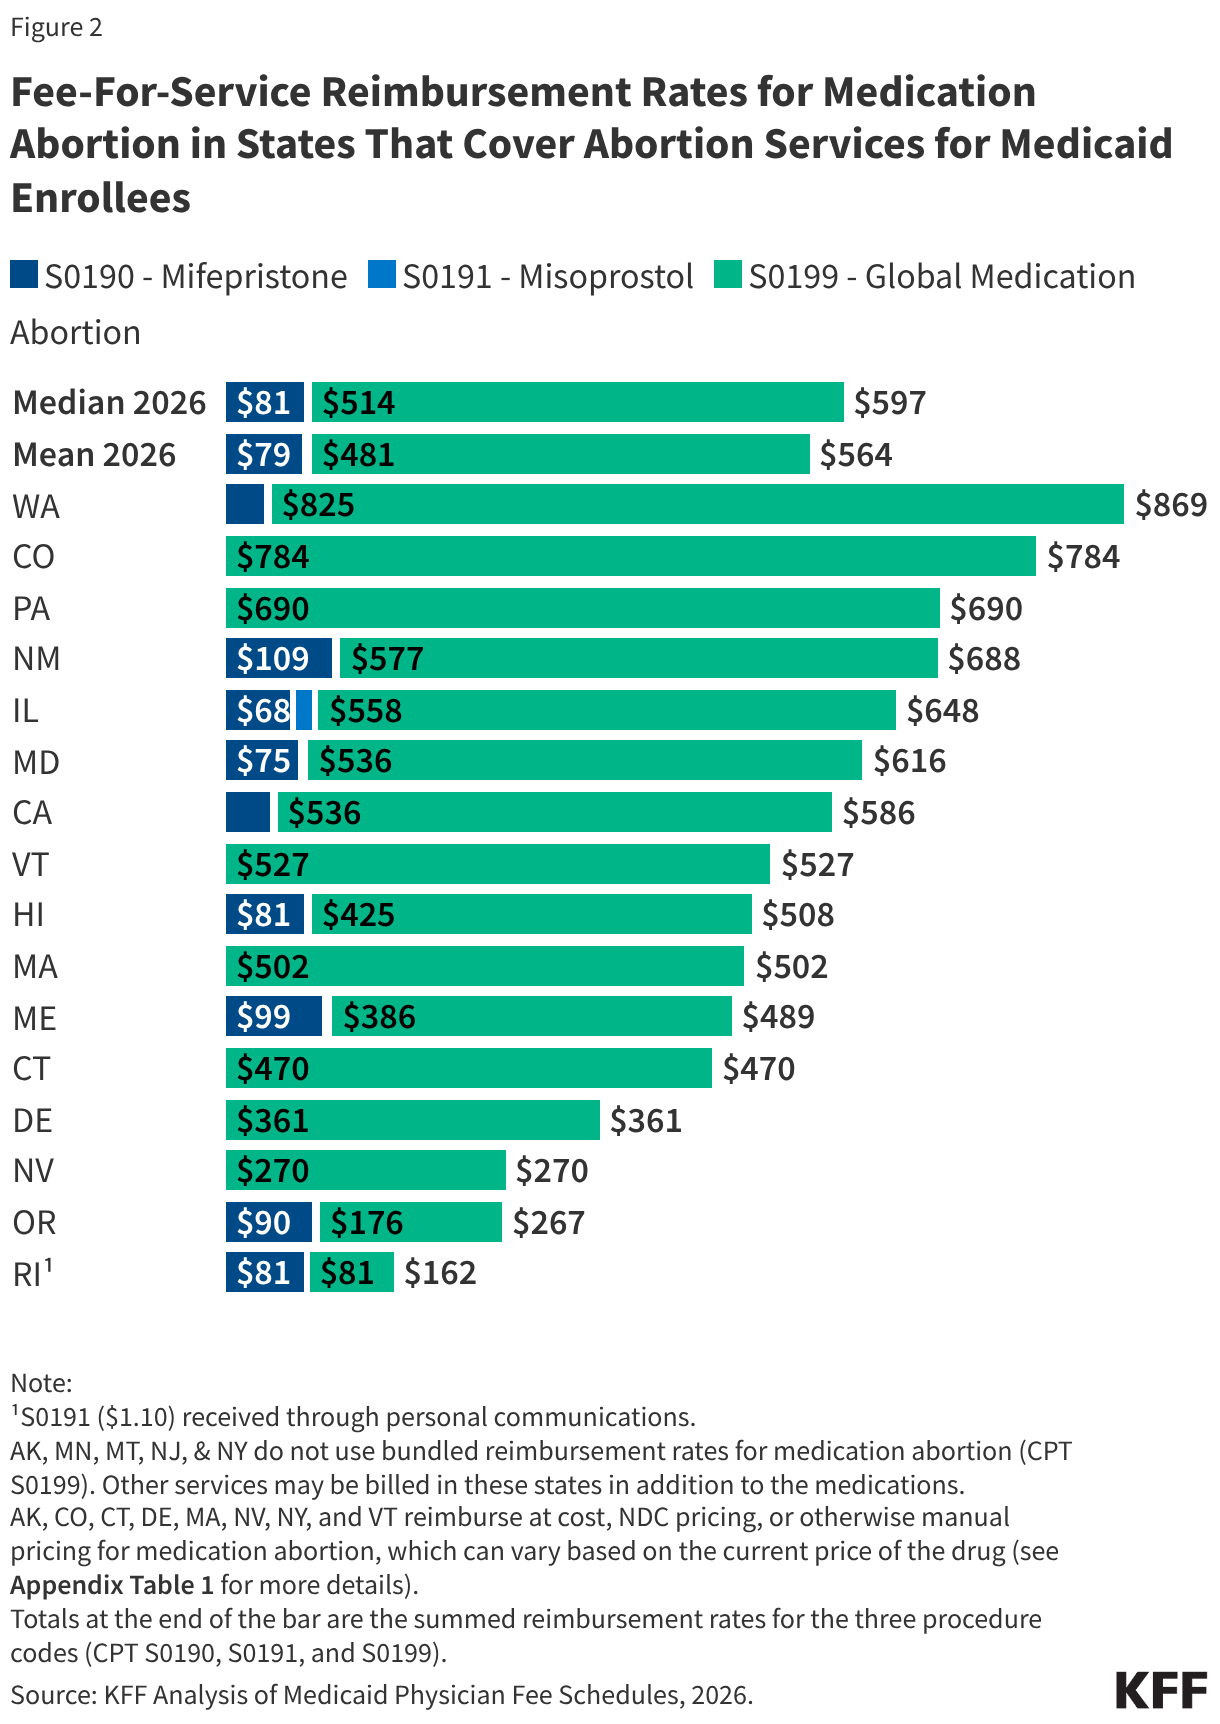
Figure 2 is a horizontal bar chart titled, “Fee-For-Service Reimbursement Rates for Medication Abortion in States That Cover Abortion Services for Medicaid Enrollees.” The chart shows Medicaid reimbursement rates for three procedure codes: S0190 (mifepristone), S0191 (misoprostol), and S0199 (global medication abortion) for 16 of  the 21 states that use state funds to cover abortion services for Medicaid enrollees and list reimbursement for the global medication abortion code. Each state's total reimbursement is shown as a stacked horizontal bar with dollar amounts labeled.

At the top, the 2026 median reimbursement totals 7, consisting of  for mifepristone and 4 for the global medication abortion code. The 2026 mean reimbursement totals 4, consisting of  for mifepristone and 1 for the global code.

Among the states shown, Washington has the highest total reimbursement at 9 and Rhode Island has the lowest at (2).

Most of the reimbursement in each state comes from the global medication abortion code, while reimbursement for mifepristone is generally much smaller, and misoprostol reimbursement is minimal or not separately shown in most states.

For the five states that do not use the bundled, global code for medication abortion, the sum of the rates for mifepristone and misoprostol alone range from $44 in Minnesota1 to $131 in New Jersey. In these states, providers may bill separately for ancillary services, which could potentially add additional reimbursement (Table 1).
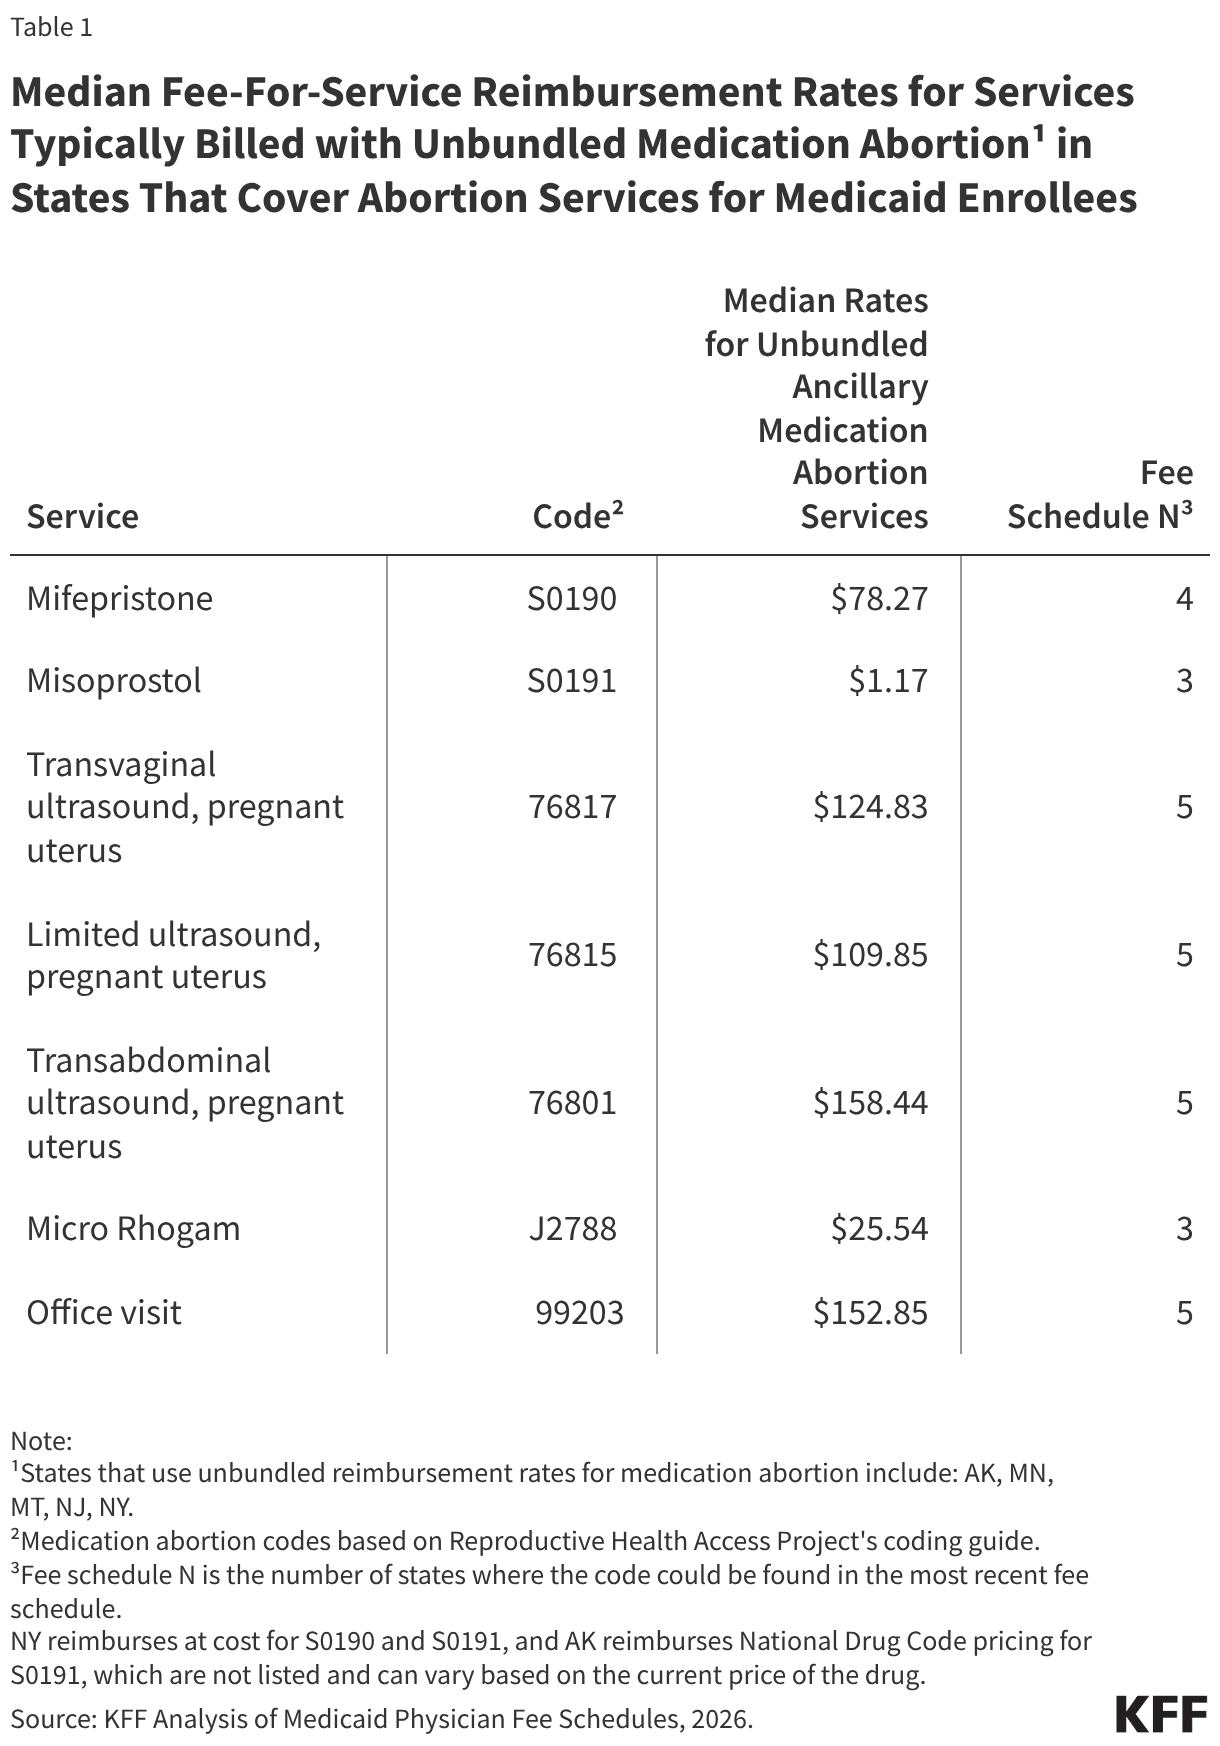
Table 1 titled, "Median Fee-For-Service Reimbursement Rates for Services Typically Billed with Unbundled Medication Abortion in States That Cover Abortion Services for Medicaid Enrollees." The table includes states that use unbundled reimbursement for medication abortion, including Alaska, Minnesota, Montana, New Jersey, and New York. The table lists medication abortion services billed alongside mifepristone and misoprostol, including transvaginal ultrasounds, limited ultrasounds, transabdominal ultrasounds, Micro Rhogam, and/or office visits. The table lists the specific billing codes, median reimbursement rates, and the number of state fee schedules used to calculate each median.

The medication abortion reimbursement rates reported in this brief apply to services provided in outpatient clinics or physicians’ offices and do not specifically address reimbursement rates for telehealth medication abortion for either bricks-and-mortar or online-only providers. Telehealth has become an increasingly common mode of medication abortion provision; in 2025, approximately 28% of all abortions were medication abortions provided through telehealth, representing a 27% overall increase from 2024. Although research on Medicaid reimbursement rates for telehealth medication abortion is limited, a 2024 report from the National Health Law Program found that, across six states (Illinois, Minnesota, New Mexico, New York, Rhode Island, and Washington), there was overall payment parity for synchronous video telehealth service delivery under Medicaid compared to in-person medication abortion service delivery. However, many of these states adopted temporary telehealth payment parity policies in response to the COVID-19 public health emergency, and some of those policies have not yet been made permanent, limiting the generalizability of these findings. 

While most states that use their own funds to pay for abortion services for Medicaid enrollees list reimbursement rates for medication abortion, only half of the states that follow Hyde restrictions list reimbursement rates for medication abortion, and median reimbursement in these states is substantially lower (see Appendix Table 1). Beyond the issue of failing to publish reimbursement rates for medication abortion, a 2025 U.S. Government Accountability Office (GAO) report found that 14 states participating in the Medicaid Drug Rebate Program (MDRP) were not complying with federal requirements to cover FDA-approved medication abortion drugs, even in circumstances permitted under the Hyde Amendment, such as rape, incest, or life-endangerment. The GAO reported these instances of noncompliance to the Centers for Medicare and Medicaid Services (CMS) in late 2025. 

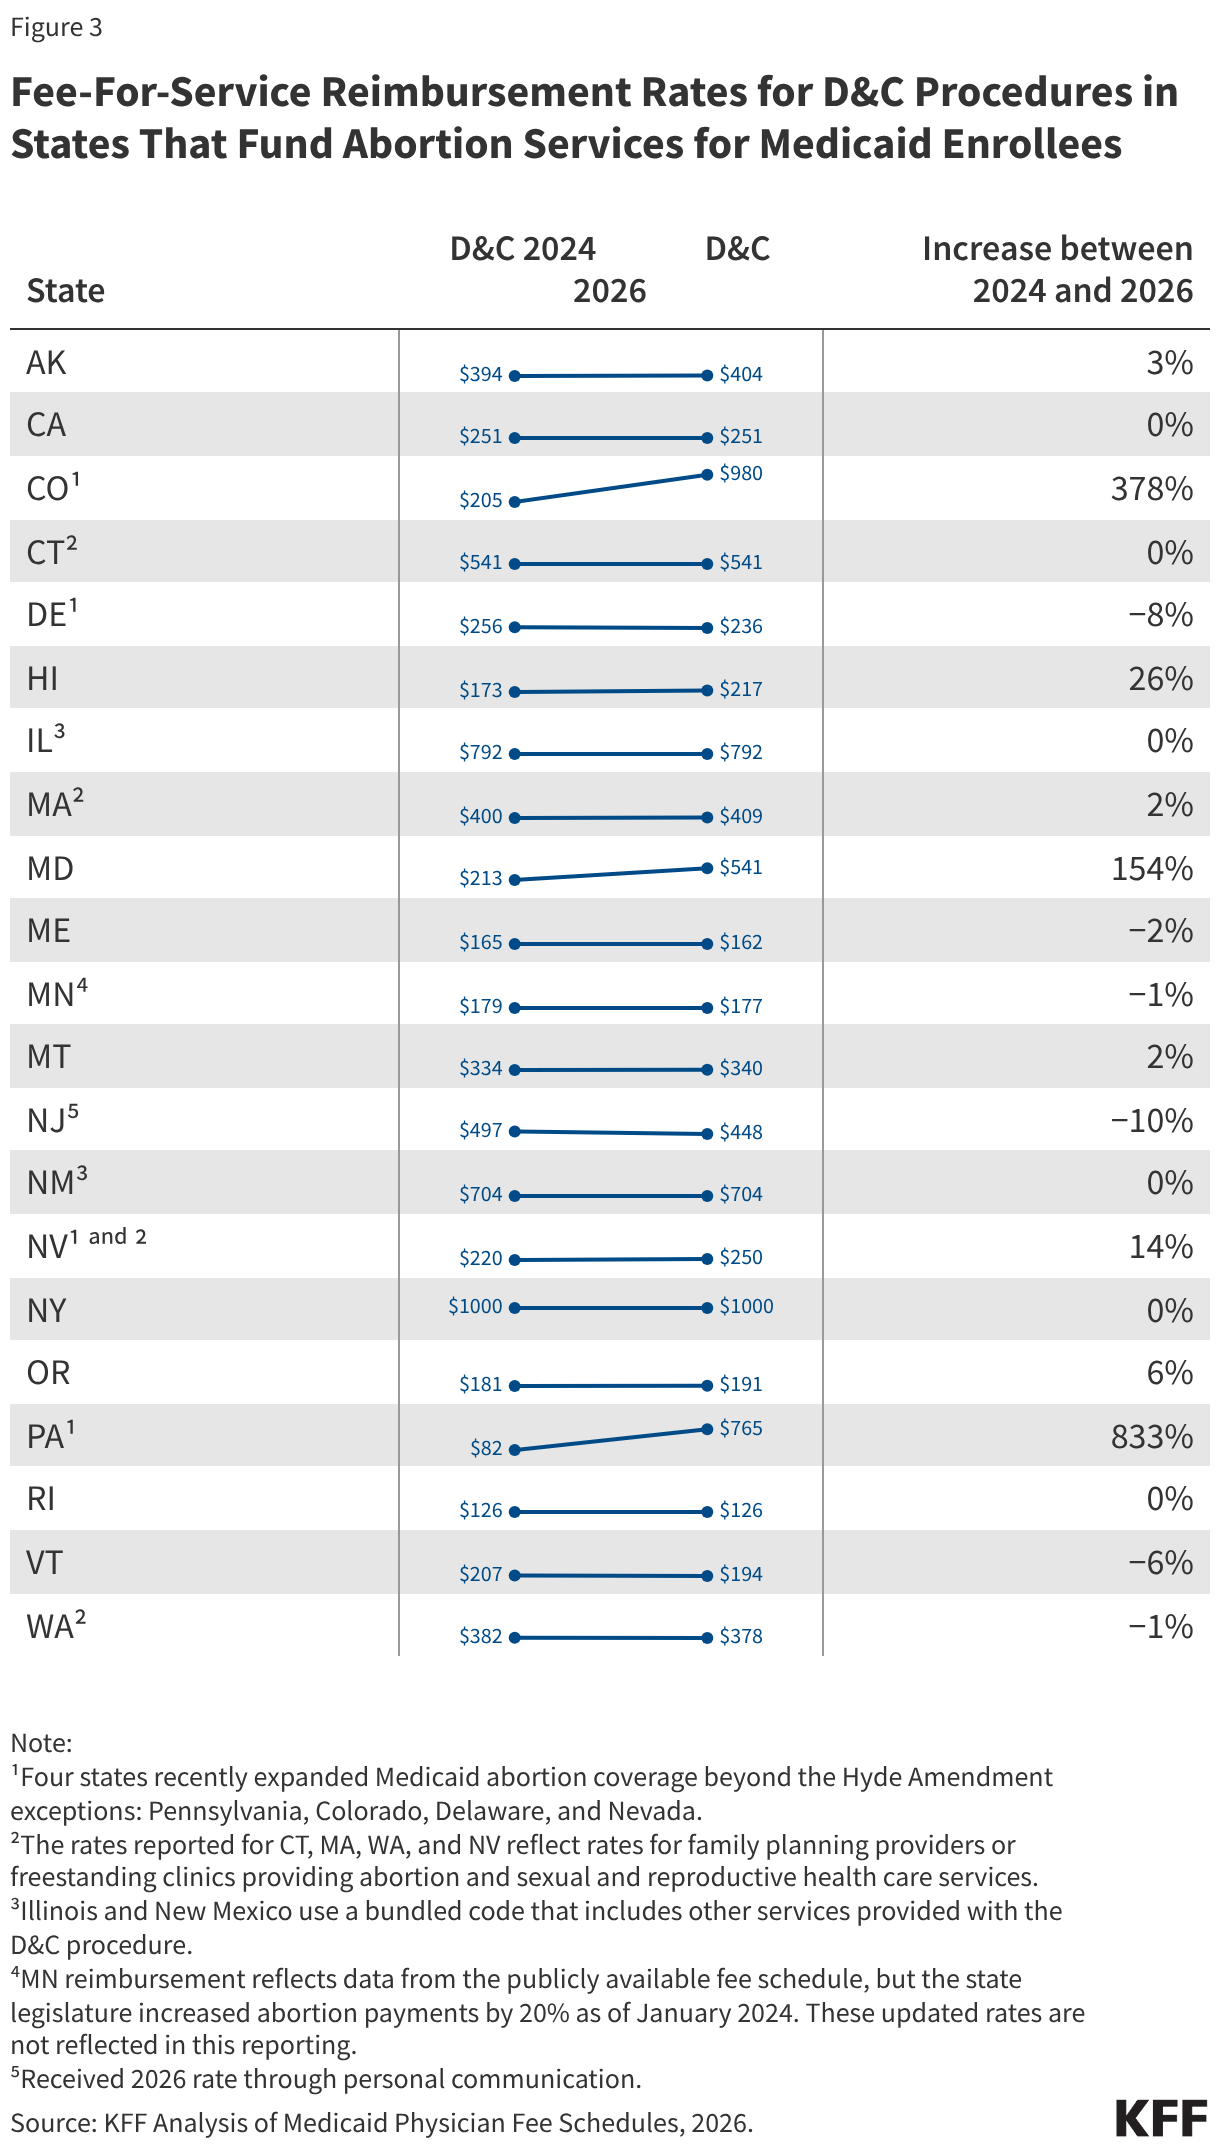
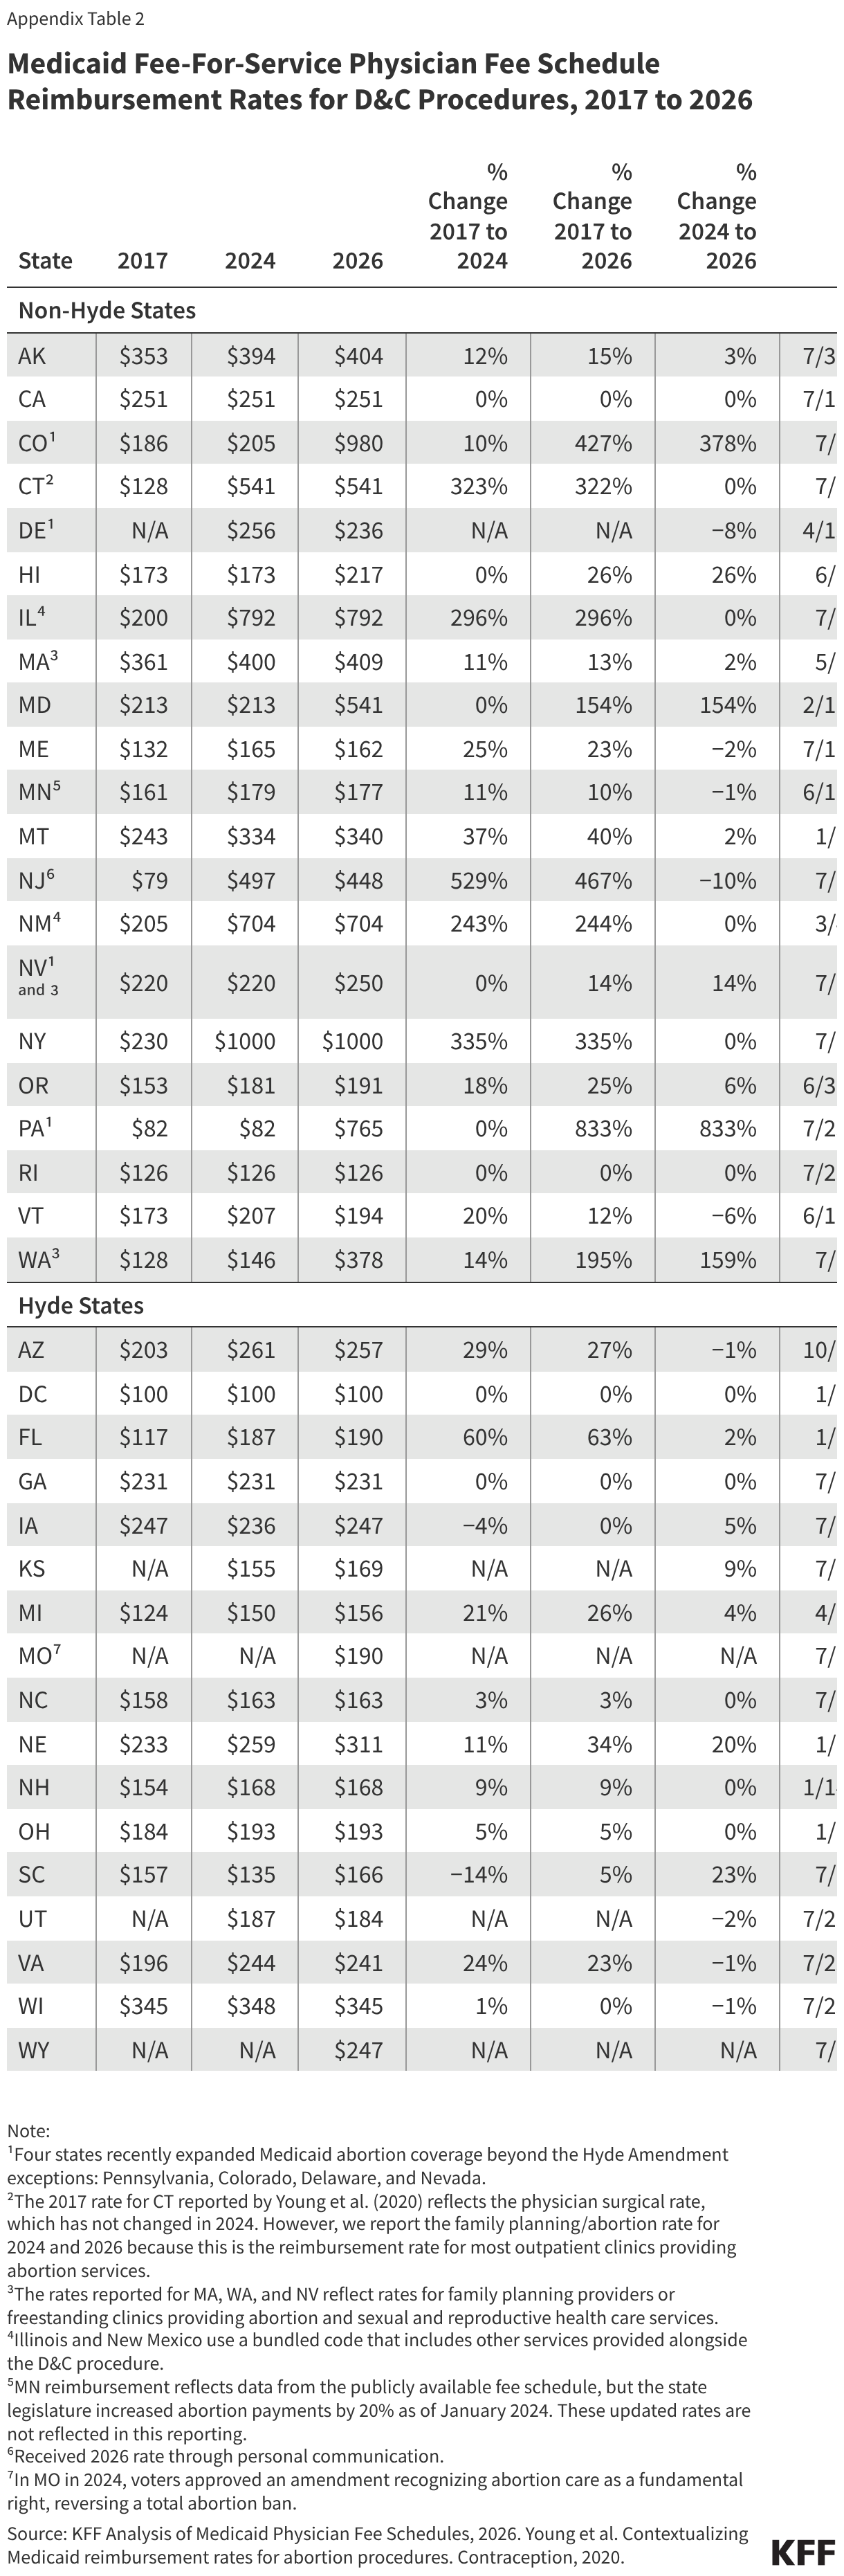
Dilation and curettage (D&C) is a common abortion procedure that can be used up to approximately 16 weeks of pregnancy. Medicaid physician fee schedules for fee-for-service reimbursement rates were published online for D&C procedures in all 21 states that use state funds to reimburse for abortion services for Medicaid enrollees beyond Hyde exceptions (Figure 3). The median reimbursement rate for a D&C procedure in these states was $378, ranging widely from $126 in Rhode Island to $1,000 in New York. Since 2024, Pennsylvania2 and Colorado have shifted from following Hyde restrictions to using state funds to pay for abortion for Medicaid enrollees. In the past two years, Pennsylvania increased their rate for D&C procedures by 833%, Colorado increased their reimbursement rate by 378%, and Maryland increased their rate by 154%. Beyond these outliers, most states have not increased their rates or increased them only slightly. Nine of 21 states that use state funds to cover abortion for Medicaid enrollees increased rates, but of those, only 5 states increased rates at or above the health care inflation rate over the past two years. Of the remaining 12 states that did not increase rates, 6 states have not changed their D&C reimbursement rates, and 6 states have decreased their rates between 2024 and 2026. In states that only reimburse for abortions in cases of pregnancies resulting from rape, incest, and life endangerment, payment rates were considerably lower (see Appendix Table 2).

Figure 3 is a table titled, "Fee-For-Service Reimbursement Rates for D&C Procedures in States That Fund Abortion Services for Medicaid Enrollees." The table lists, by state, Medicaid reimbursement rates for dilation and curettage (D&C) abortion procedures in 2024 and 2026 and includes a line graph depicting the change in rates over the two time periods. It also includes a percentage change column that ranges from -10% in New Jersey (7 to 8) to 833% in Pennsylvania ( to 5) that recently started using state funds to pay for abortion services for Medicaid enrollees.

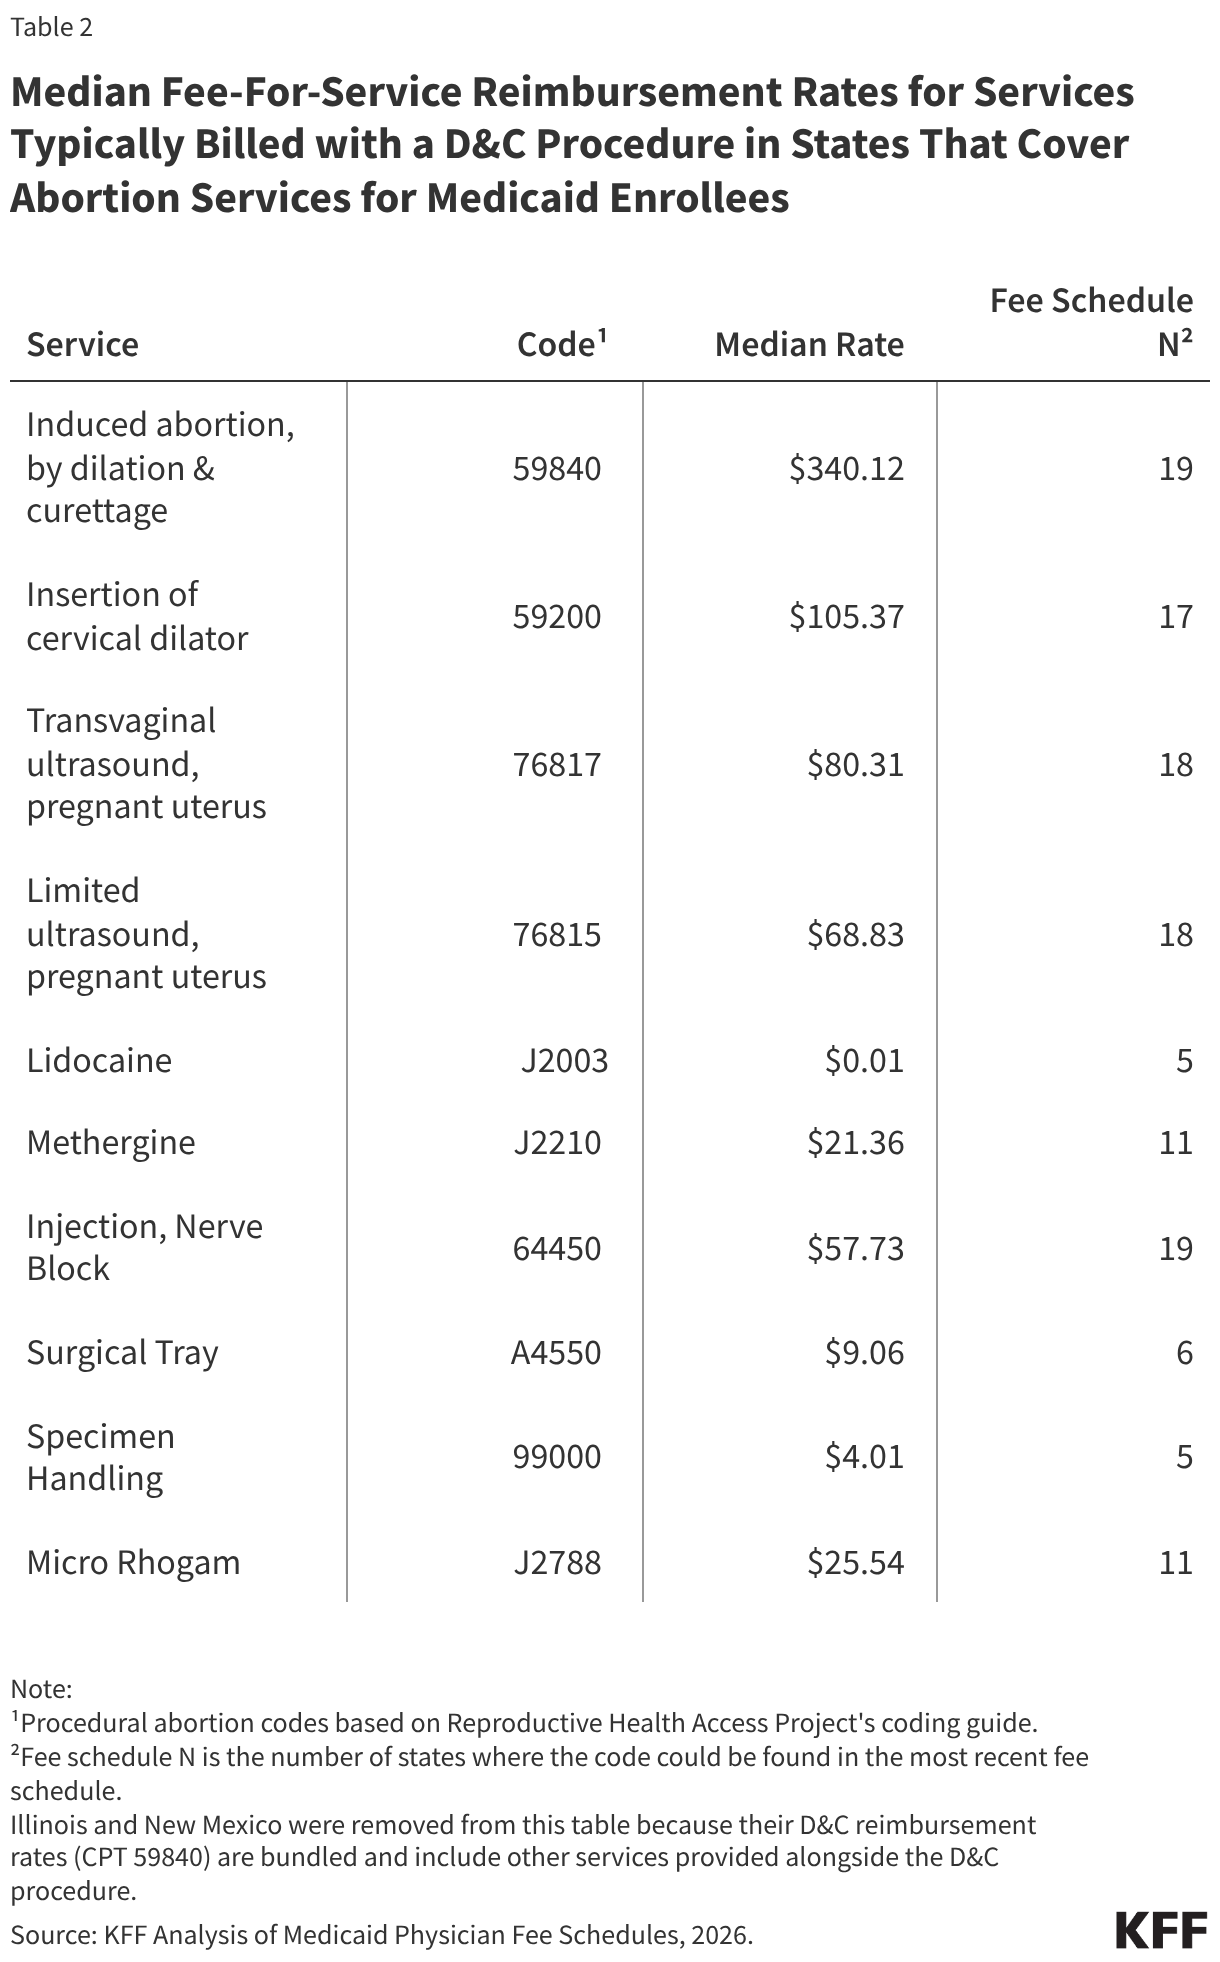
Other services may be billed and reimbursed on the day of a procedural abortion including ultrasound, anesthetic medication administration like lidocaine and methergine, or a nerve block for pain. In some states, the reimbursement rates for these additional services are not publicly posted (Table 2). Illinois and New Mexico reimburse procedural abortions (CPT codes 59840 and 59841) as bundled codes and will not pay for other related services when these codes are billed. Therefore, Illinois and New Mexico were removed from the calculations in the table below detailing median ancillary rates for services that may be provided at the time of the abortion. 

Table 2 is titled, "Median Fee-For-Service Reimbursement Rates for Services Typically Billed with a D&C Procedure in States That Cover Abortion Services for Medicaid Enrollees." The table lists dilation and curettage abortion services billed alongside D&C procedures, including insertion of cervical dilator, transvaginal ultrasound, limited ultrasound, lidocaine, methergine, nerve block injection, surgical tray, specimen handling, and Micro Rhogam. The table lists the billing codes associated with those services, median reimbursement rates, and the number of state fee schedules included to calculate each median.

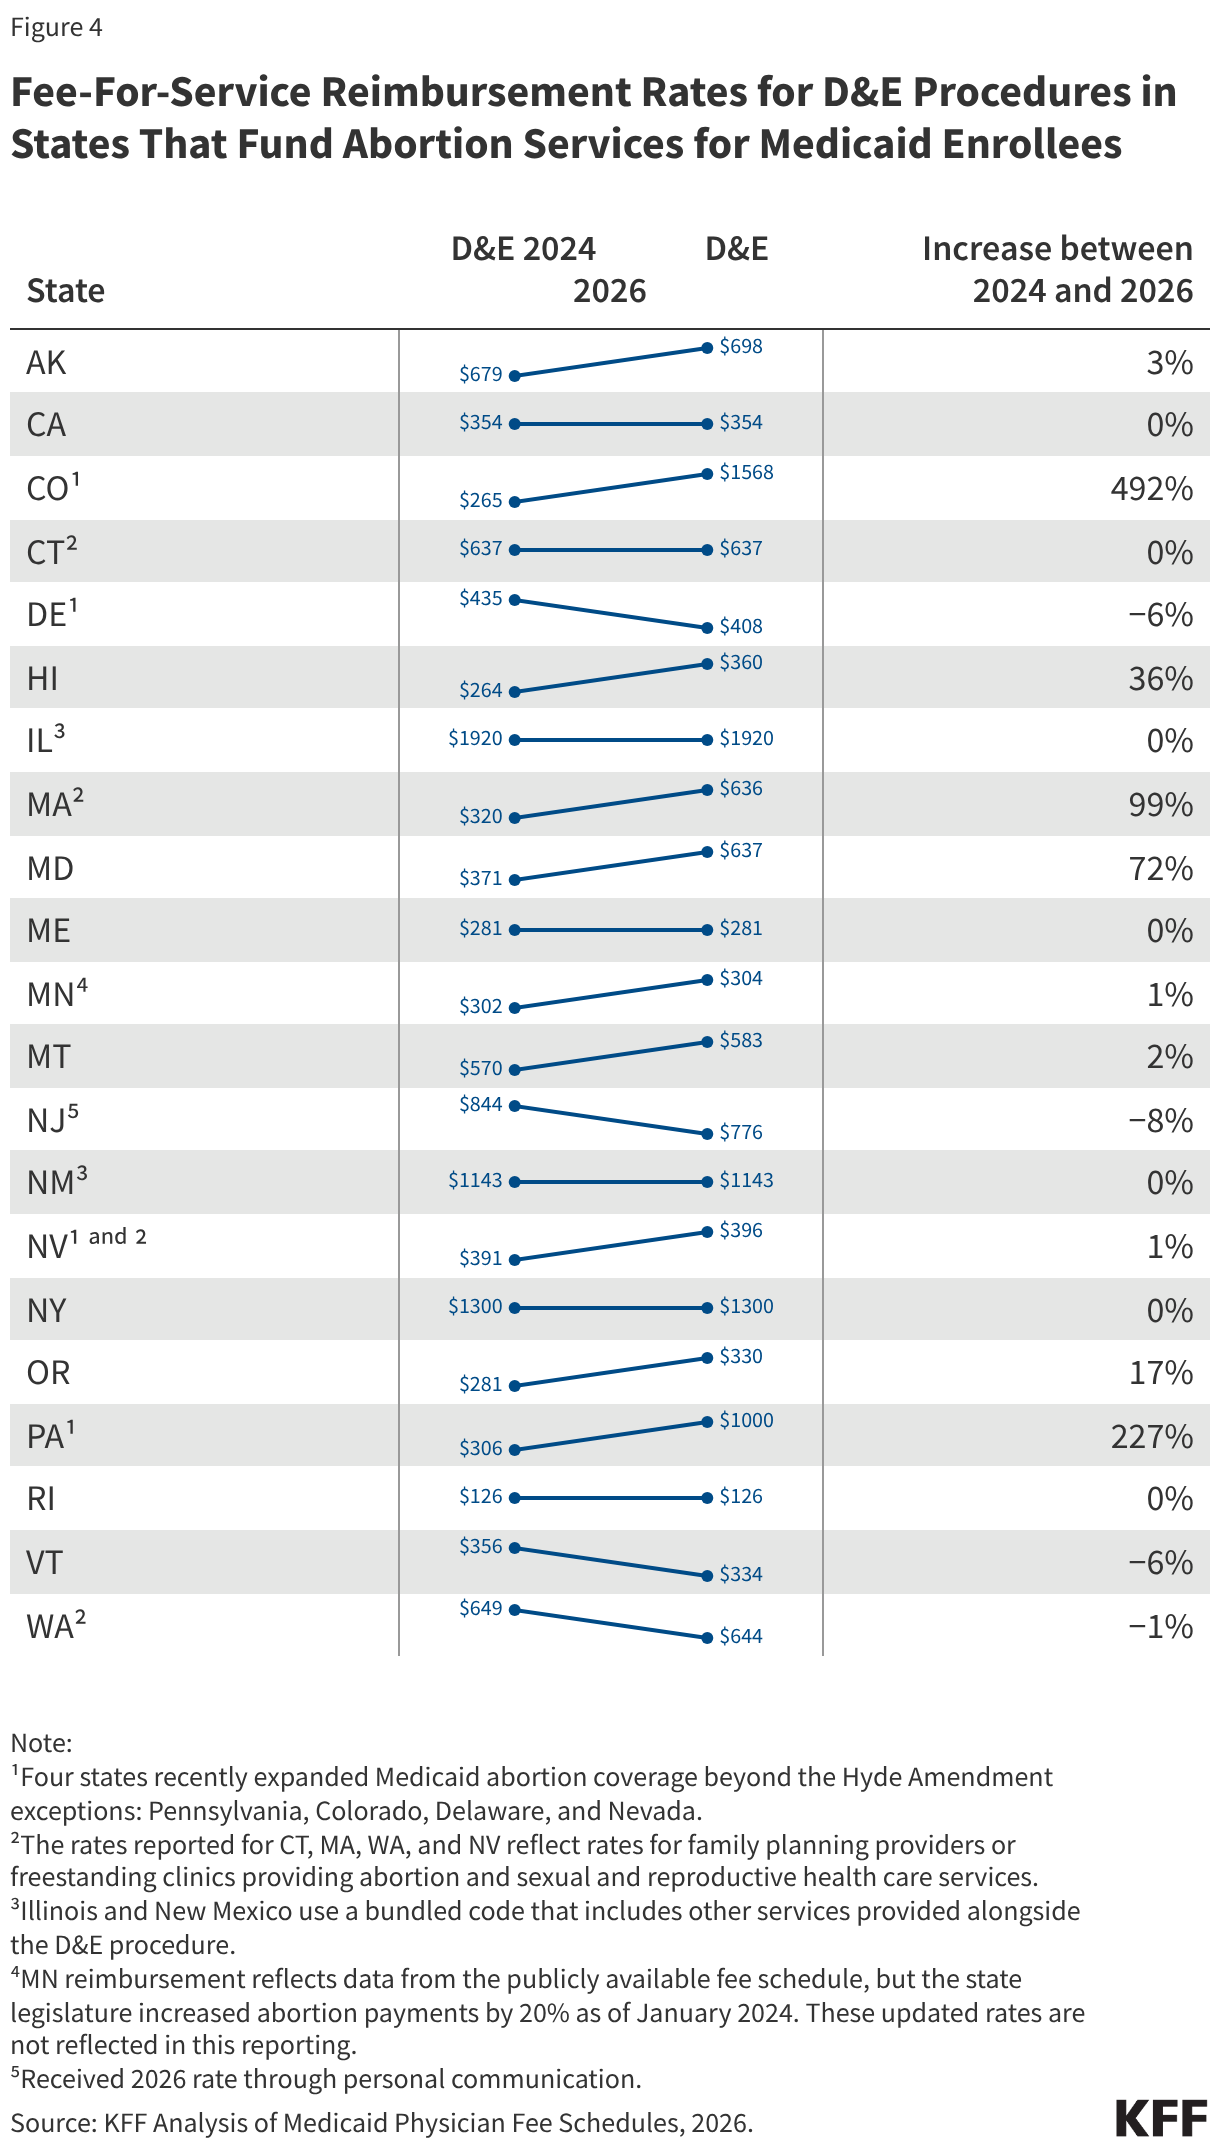
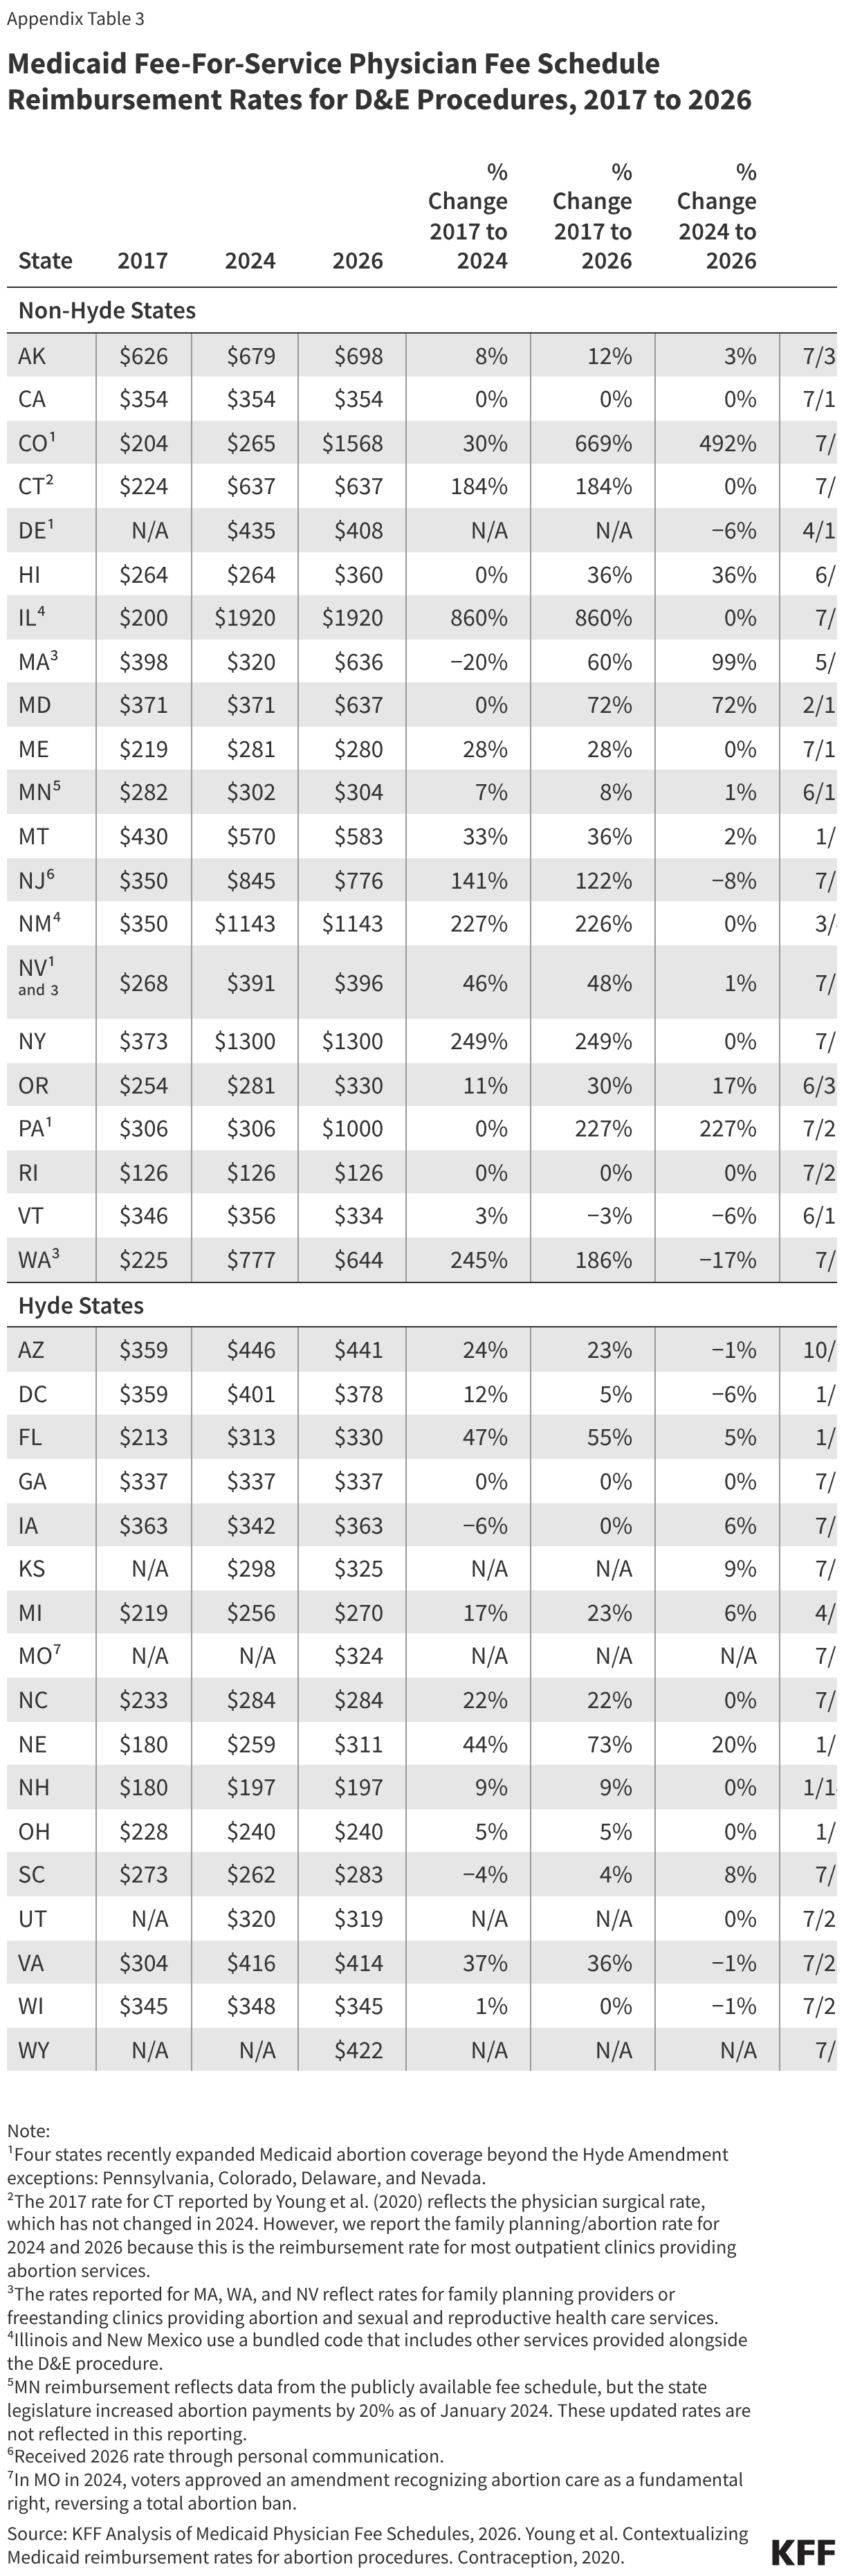
For a dilation and evacuation (D&E) procedure, which is often used in the second trimester, the reimbursement rates similarly varied widely by state (Figure 4). In states that fund abortion services for Medicaid enrollees, the median reimbursement rate for a D&E procedure was $636, ranging from a low of $126 in Rhode Island to a high of $1,920 in Illinois. Since 2024, Colorado increased their D&E reimbursement rate by 492%, Pennsylvania increased their rate by 227%, and Massachusetts by 99%. Beyond those substantial reimbursement rate increases, 10 of 21 states that use state funds to pay for abortion for Medicaid enrollees increased D&E reimbursement rates for Medicaid providers between 2024 and 2026, but only 6 increased their rates at or above the rate of health care inflation. Of the remaining 11 states that did not increase rates, 7 have not changed their D&E reimbursement rates, and 4 have decreased their rates over the past two years. As with D&C procedures, the median reimbursement rate for D&E procedures in states that pay for abortions for Medicaid enrollees is higher than in states that limit abortion coverage to those cases permissible under the Hyde Amendment (see Appendix Table 3).

Figure 4 is a table titled, "Fee-For-Service Reimbursement Rates for D&E Procedures in States That Fund Abortion Services for Medicaid Enrollees." The table lists, by state, Medicaid reimbursement rates for dilation and evacuation (D&E) abortion procedures in 2024 and 2024 and includes a line graph depicting the rate of change over the two time periods.  It also includes a percentage change column that ranges from -8% in New Jersey (4 to 6) to 492% in Colorado (5 to 68), which recently started using state funds to pay for abortion services for Medicaid enrollees.

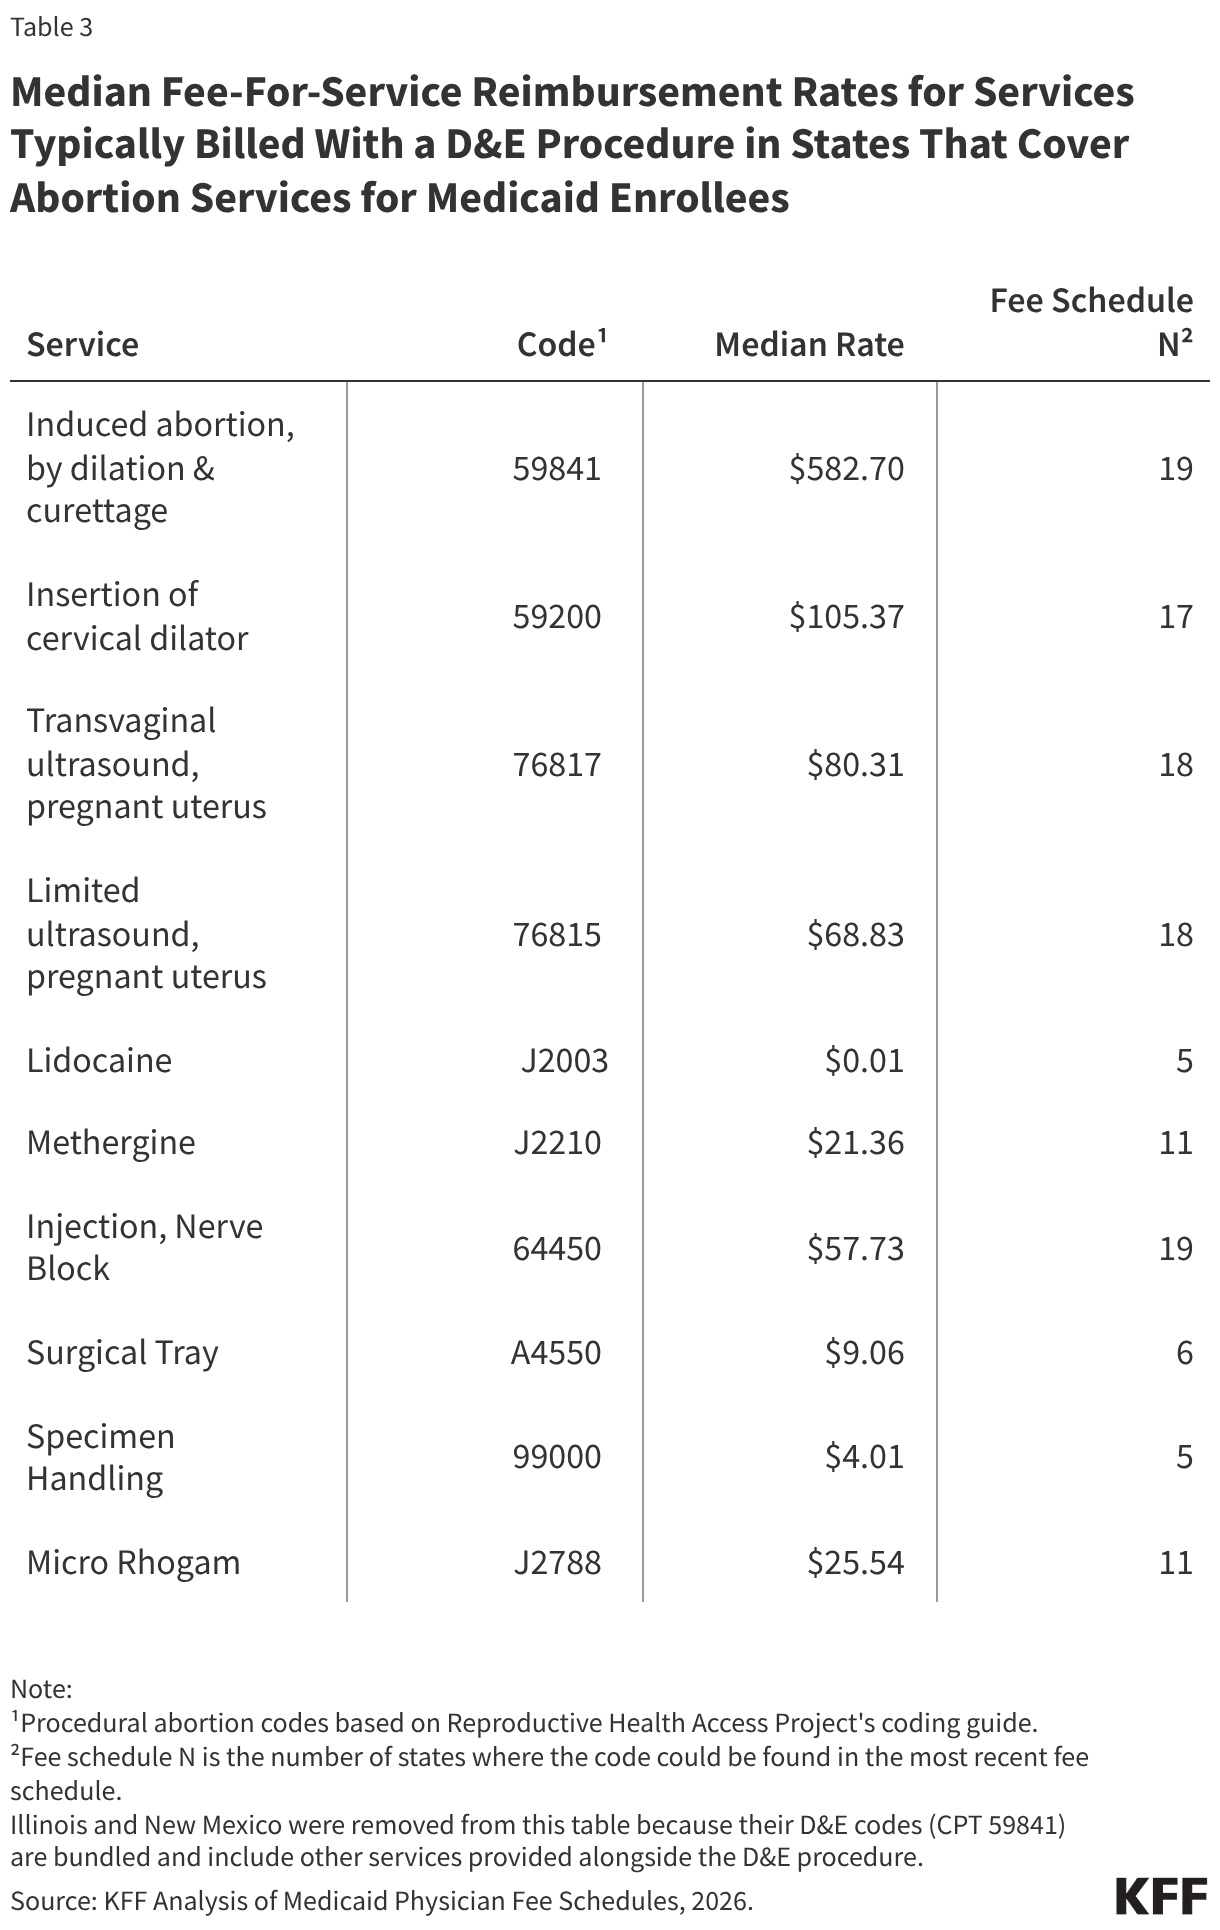
As with D&C procedures, providers will often bill for other services provided with the D&E procedure if the code is not a bundled code (Table 3). In line with D&C procedures, Illinois and New Mexico use bundled rates for D&E procedures that include ancillary services and, therefore, are not included in the calculations in the table below.  

Table 3 is titled, "Median Fee-For-Service Reimbursement Rates for Services Typically Billed with a D&E Procedure in States That Cover Abortion Services for Medicaid Enrollees." The table lists common dilation and evacuation abortion services billed alongside D&E procedures, including insertion of cervical dilator, transvaginal ultrasound, limited ultrasound, lidocaine, methergine, nerve block injection, surgical tray, specimen handling, and Micro Rhogam. The table lists the billing codes associated with those services, median reimbursement rates, and the number of state fee schedules included to calculate each median.

Abortion Financing, Cost, and Medicaid Policy Considerations

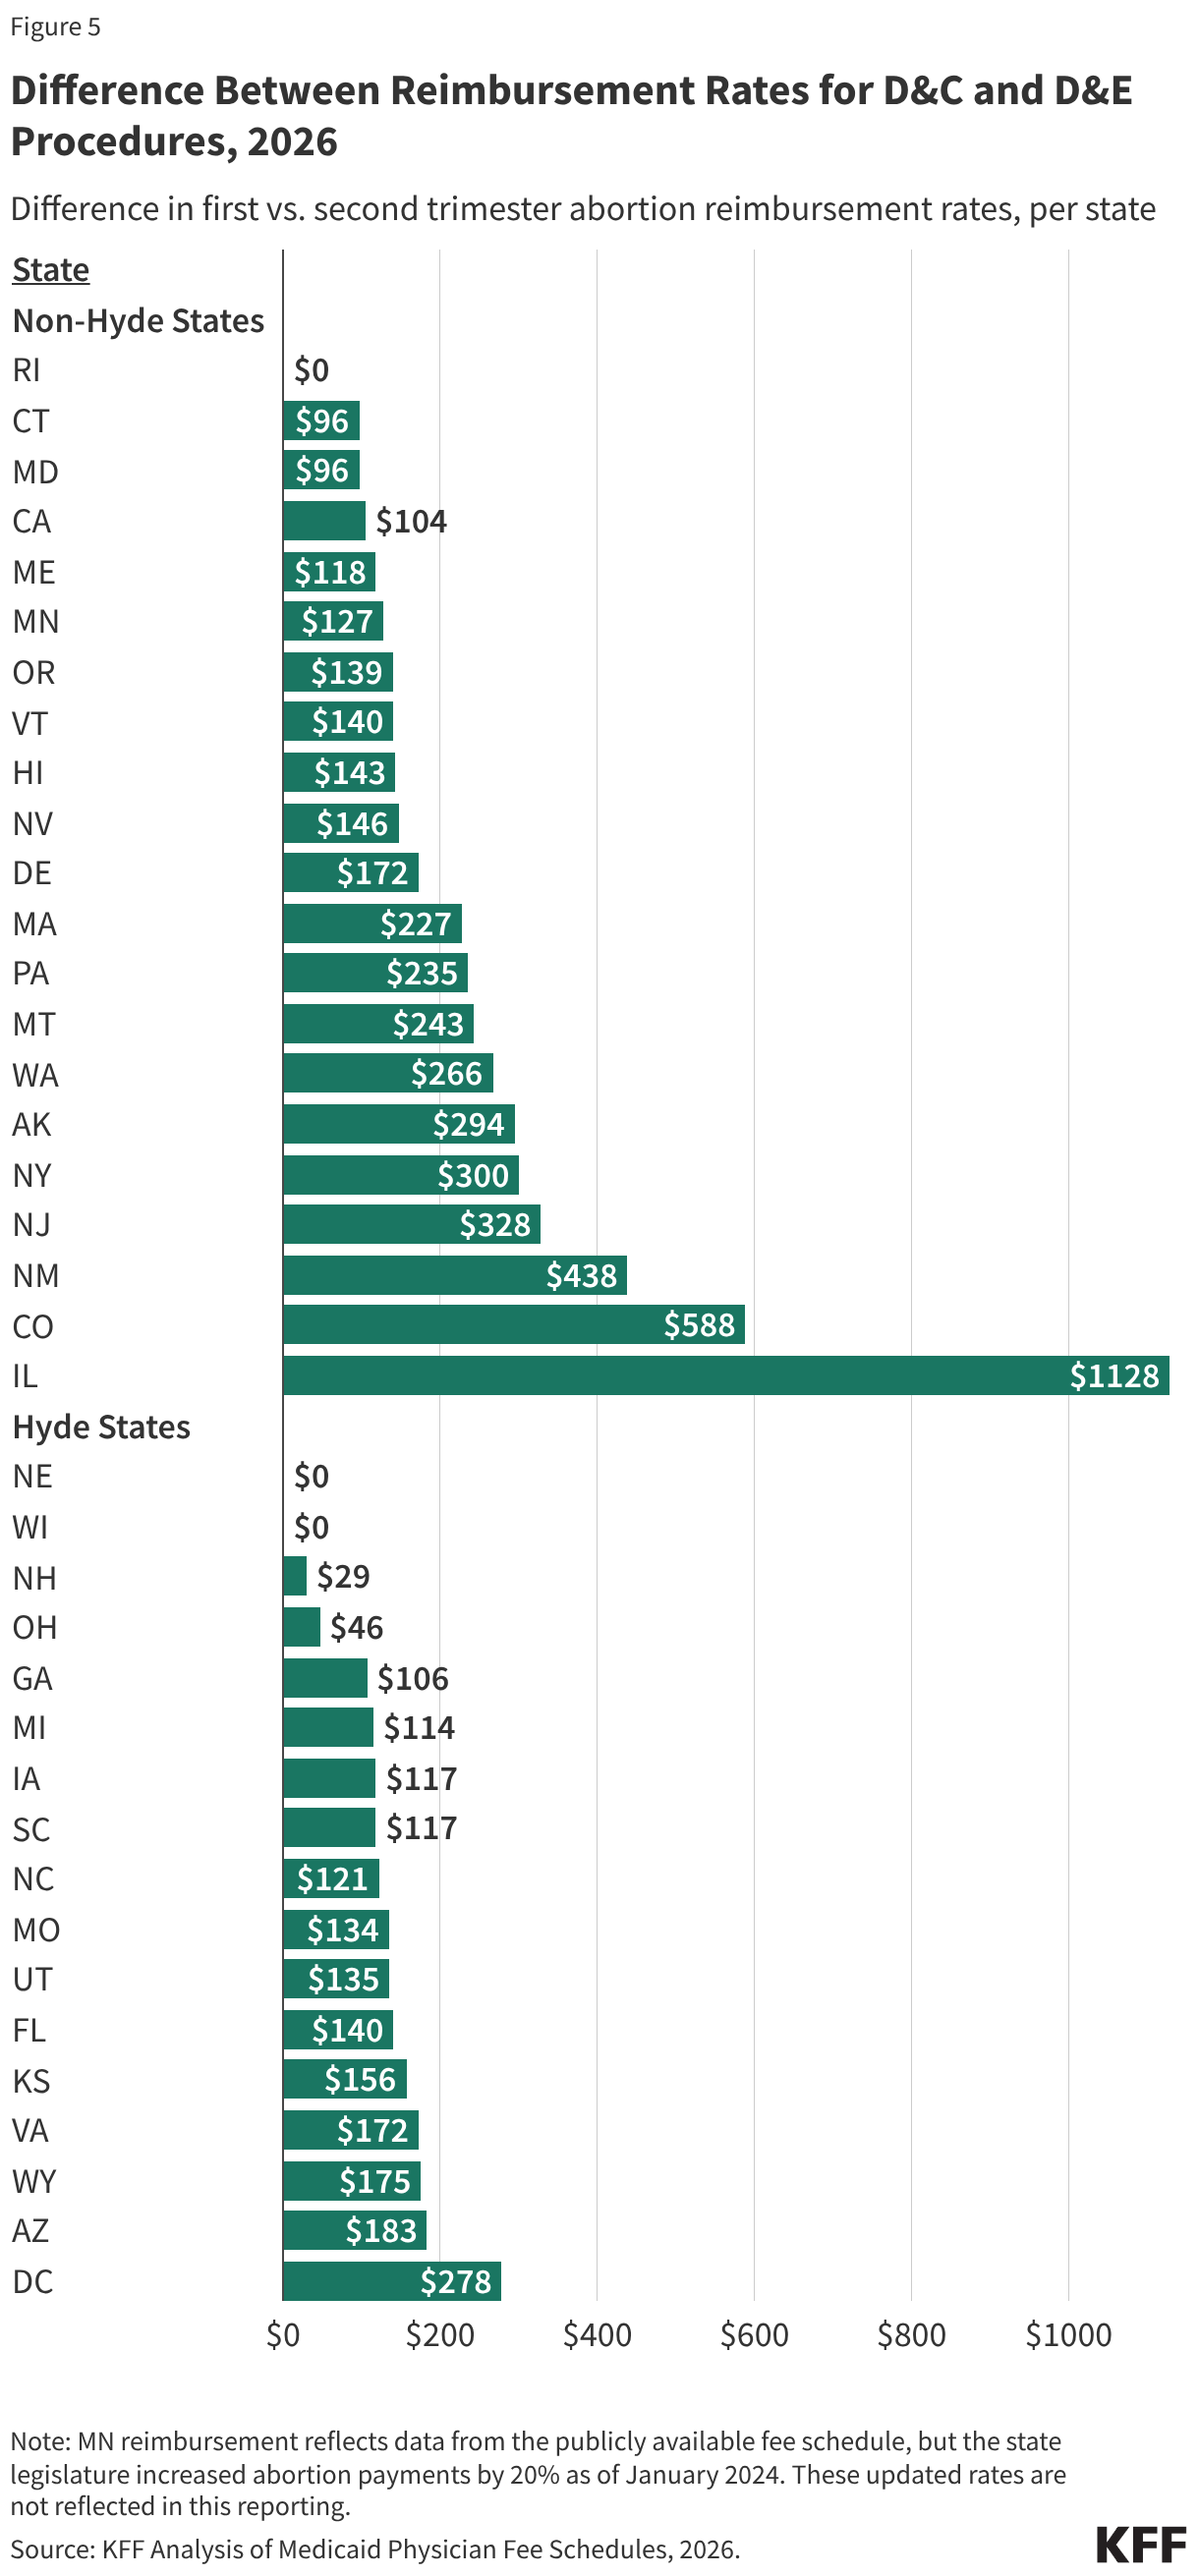
Given that D&E procedures are typically provided later in pregnancy and are more costly and complex procedures, it would follow that reimbursement would be substantially higher than for D&C procedures, which are typically done earlier in pregnancy. The majority of states (27 of 38) without bans—including Hyde and non-Hyde states—reported a Medicaid reimbursement rate difference that was less than $200 (Figure 5). Three states (Rhode Island, Nebraska, & Wisconsin) reimburse for first and second trimester abortions at the exact same rate, failing to account for the differences in cost and complexity of these different procedures, leaving providers to either be exposed to financial losses if they provide abortions later in pregnancy or decline to accept Medicaid patients.

Figure 5 is a horizontal bar chart titled, “Difference Between Reimbursement Rates for D&C and D&E Procedures, 2026.” The chart compares Medicaid reimbursement rate differences in first and second trimester abortions per state, split up by Non-Hyde and Hyde states. Non-Hyde states range from reimbursement rate differences from alt=

In analyzing the role of Medicaid in abortion financing, the Guttmacher Institute’s 2021-2022 Abortion Patient Survey found 62% of abortion patients living in states that funded abortion beyond Hyde restrictions used Medicaid to pay for their abortion. Comparatively, for abortion patients living in Hyde restricted states, 82% paid out of pocket for their care, with two-thirds of those surveyed reporting they had to raise money to afford their abortion, often through accruing debt, relying on financial subsidies from abortion funds or clinic discounts, or asking friends and family. Abortion funds have long been relied on as a safety-net option for those in need of assistance in paying for their abortion, but a post-Dobbs trend of increased requests for support coupled with decreased donations leaves funds in precarious and depleted financial positions.  

These disparities in how abortion care is financed highlight the fact that insurance coverage alone is insufficient to assure access, particularly when providers’ reimbursement policies inadequately support the costs of the full range of abortion services. While reimbursement for care after the second trimester is not directly addressed in this report, a recent study investigated self-pay prices paid by patients seeking later abortion care and found that prices increased with gestational stage, while, inversely, provider and clinic availability and Medicaid coverage declined. Low Medicaid reimbursement for these services may further exacerbate reproductive access inequities for Medicaid enrollees.  

Beyond implications on patient affordability, reimbursement rates also affect providers’ ability to provide abortions to all patients regardless of payor. As with all health services, the cost of providing abortions has grown in all states as the costs of medical equipment and personnel increase annually. In addition, abortion providers face expenses that are not incurred by most other outpatient clinics such as security costs to keep their staff and patients safe from anti-abortion activities, such as extra security guards, cameras, staff background checks, and bulletproof windows. Increased safety concerns and costs have also made it difficult to retain the abortion clinic workforce.  

Appendix table 1 is titled, "Medicaid Fee-For-Service Physician Fee Schedule Reimbursement Rates for Medication Abortion, 2026." The table lists, by state (split into Non-Hyde and Hyde States) reimbursement rates for S0190 (mifepristone), S0191 (misoprostol), and S0199 (global medication abortion), and a link to each state's Medicaid physician fee schedule.
Appendix table 2 is titled, "Medicaid Fee-For-Service Physician Fee Schedule Reimbursement Rates for D&C Procedures, 2017 to 2026." The table lists, by state (split into Non-Hyde and Hyde States) reimbursement rates for D&C (CPT code 59840) in 2017, 2024, and 2026, includes the percent change from 2017 to 2024, 2017 to 2026, and 2024 to 2026, and a link to each state's Medicaid physician fee schedule.
Appendix table 3 is titled, "Medicaid Fee-For-Service Physician Fee Schedule Reimbursement Rates for D&E Procedures, 2017 to 2026." The table lists, by state (split into Non-Hyde and Hyde States) reimbursement rates for D&E (CPT code 59841) in 2017, 2024, and 2026, includes the percent change from 2017 to 2024, 2017 to 2026, and 2024 to 2026, and a link to each state's Medicaid physician fee schedule.

A prior version of this brief was originally posted March 2024. If interested in a copy of the prior brief, please to write to womenshealth@kff.org.

  1. MN reimbursement reflects data from the publicly available fee schedule, but the state legislature increased abortion payments by 20% as of January 2024. These updated rates are not reflected in this reporting.  ↩︎
  2. Under the recent Commonwealth Court ruling, Pennsylvania Medicaid is legally required to cover abortion care as of July 15, 2026. However, the Pennsylvania Department of Human Services (DHS) is still in the process of establishing the necessary billing and reimbursement system to process coverage. ↩︎

The Trump Administration’s Foreign Aid Review: Status of U.S. Global Tuberculosis Efforts

Published: Aug 6, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on U.S. Global Tuberculosis (TB) Efforts

  • The U.S. government has been involved in global TB activities for decades and began ramping up its efforts in the late 1990s when a global TB program was created. The U.S. had been the top donor to TB efforts.
  • TB, an infectious disease caused by bacteria, causes more deaths than any other infectious agent worldwide, including 1.23 million people who died in 2024, and is among the 10 leading causes of death worldwide. TB is the leading cause of death among people with HIV.
  • Recent decades have seen improvement, and U.S. government investments have contributed significantly to improving TB health outcomes, including an almost 25% decline in TB incidence between 2000 and 2023, and a significant drop in TB deaths.  
  • Prior to its dissolution in 2025, USAID had served as the lead implementing agency for U.S. global TB efforts, focusing on 24 priority countries – with activities in 50 (including at least 20 of the 30 high burden countries) – to support prevention, detection, and treatment of TB, including drug-resistant TB. The Centers for Disease Control and Prevention (CDC) also had carried out global TB efforts, and the State Department’s Bureau of Global Health Security and Diplomacy (GHSD), which oversees PEPFAR, leads U.S. efforts to address TB-HIV co-infection.
  • Prior to the start of the Trump administration, U.S. funding for global bilateral TB activities in FY 2024 was $406 million; funding for the Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund) was $1.65 billion.                                                    

Current Status of U.S. Global TB Efforts

The following administration actions have had a significant impact on TB program operations:

  • Stop-work order: The stop-work order initially froze all bilateral TB programming and services, halting existing work in the field. Because it halted payments, many implementers had to terminate staff and end some services.
  • Limited waiver: Some TB activities were included in a limited waiver issued by the State Department on February 4, 2025, allowing “life-saving services” to continue, which are defined as “Essential screening, testing, and treatment for tuberculosis (TB) and drug resistant TB (DR-TB) including provision and monitoring of laboratory services, drug susceptibility testing, clinical visits, dispensing of essential medicines to avert near-term mortality and spread of infection.” HIV/TB activities were also allowed under PEPFAR’s limited waiver. Even with the waivers, services remained disrupted and implementers faced challenges in getting permission to resume programming and difficulties in getting paid.
  • Dissolution of USAID: As the main government implementer of TB efforts, the dissolution of USAID and loss of most staff have significantly affected TB program implementation capacity and operations. Without USAID and most of its staff, TB efforts’ implementation capacity and operations have been affected. In addition, announcements of reductions at CDC could further affect global TB efforts.
  • Canceled awards: In early 2025, it was reported that the administration canceled 86% of all USAID awards. KFF analysis found that of the 770 global health awards identified, 162 included TB activities, 79% of which were terminated.
  • Legal actions: In response to two lawsuits filed against the administration’s actions, a federal judge issued a preliminary injunction ordering the government to pay for work completed by February 13, 2025, although not all payments have been made and the court did not stop the government from canceling awards. The government appealed the ruling and after several subsequent rulings in the case, the Supreme Court ultimately allowed the government to rescind (cancel) a portion of expiring global health funds before the end of the fiscal year. Further proceedings have been stayed, pending the outcome of a separate case.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and that any remaining USAID operations would be absorbed by the State Department with global health activities, including for TB, to be integrated into its Bureau of Global Health Security and Diplomacy (GHSD) which oversees PEPFAR. On May 29, 2025, the State Department further notified Congress of its proposed reorganization plan, and with the dissolution of USAID, programs moved in July 2025.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. TB has been included in some of the agreements signed to date, although there is little information available on activities and funding.
  • Policy restrictions: In January 2025, the Trump administration reinstated the expanded Mexico City Policy from Trump’s first term and further expanded it in January 2026 to apply to almost all non-military foreign assistance, many more entities, and additional areas of restrictions including activities related to diversity, equity and inclusion and “gender ideology” under a broader umbrella known as the “Promoting Human Flourishing in Foreign Assistance” (PHFFA) Policy.
  • Funding: The Trump administration has requested significantly less funding for TB in its budget requests and canceled funding for numerous TB-related projects and awards. Despite this, Congress has continued to appropriate funding for bilateral global TB activities at close to prior year levels, including $390 million (at the State Department and CDC) in FY 2026. It also appropriated $1.25 billion for contributions to the Global Fund in FY 2026.

Impact on Global TB Services and Outcomes

  • An internal USAID memo from 2025 estimated that the cessation of USAID’s TB control programs could increase global TB incidence by 28-32% and have a similar effect on new cases of multi-drug-resistant TB.
  • According to WHO, the 30 highest TB-burden countries reported in 2025 that U.S. funding withdrawals were affecting services, including the loss of thousands of health workers, and disruptions of the drug supply chain and laboratory services.
  • A rapid assessment survey of 108 WHO country offices in 2025 found that approximately 40% reported moderate or severe disruptions to TB services, including for medicines and health products, due to the U.S. foreign aid freeze and other shortages. A more recent 2025 WHO survey found that among 17 high-burden countries, 11 reported that cuts in external support undermined TB-related community engagement and TB screening efforts, 7 reported an impact on TB preventive treatment, and 3 reported an impact on TB treatment.
  • In addition, several modeling studies have found that cuts in or termination of U.S. TB funding could result in significant increases in TB cases and deaths, and greater economic burden on households, in coming years.

What to Watch

  • Implementation of the America First Global Health Strategy multi-year agreements with countries
  • Status of U.S. funding appropriated by Congress for bilateral TB efforts and contributions to the Stop TB Partnership and the Global Fund
  • Impact of the PHFFA Policy on U.S. funding and programs
  • Impact of U.S. changes to global health programs on health outcomes

The Trump Administration’s Foreign Aid Review: Status of PEPFAR

Published: Aug 6, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on PEPFAR

  • The U.S. President’s Emergency Plan for AIDS Relief (PEPFAR), first authorized in 2003, is the largest commitment by any nation to address a single disease, working in more than 50 countries and the U.S. has been the top donor to HIV efforts, through PEPFAR and contributions to the Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund).
  • PEPFAR is credited with having saved 26 million lives and enabling 7.8 million babies to be born without HIV infection. Studies have also found that PEPFAR funding is associated with several “spillover” effects including significant reductions in all-cause mortality, increases in childhood immunizations and in GDP growth, and retention of children in school.
  • PEPFAR has been reauthorized by Congress four times, most recently in March 2024 for one year. Although that authorization expired on March 25, 2025, PEPFAR is a permanent part of U.S. law and, other than a set of eight time-bound provisions, continues as long as Congress appropriates funding.
  • PEPFAR, per its authorizing statute, is to be overseen by a U.S. Global AIDS Coordinator, a Senate-confirmed position appointed by the President and holding the rank of ambassador, at the State Department’s Bureau of Global Health Security and Diplomacy (GHSD). GHSD is charged with coordinating its implementation through other government agencies (primarily USAID – before its dissolution – and CDC) and, historically, with implementing partners, civil society, and recipient countries.
  • Prior to the start of the Trump administration, U.S. funding for PEPFAR in FY 2024 was $4.9 billion; funding for the Global Fund was $1.65 billion.

Current Status of PEPFAR

The following administration actions have had a significant impact on PEPFAR operations:

  • Stop-work order: The stop-work order initially froze all PEPFAR programming and services, halting existing work in the field, including provision of antiretroviral therapy. Because it halted payments, many implementers had to terminate staff and end some services.
  • Limited Waiver: PEPFAR received a limited waiver on February 1, 2025 (with additional information on February 6, 2025), allowing it to continue “life-saving HIV services”. However, the waiver only permitted certain activities: HIV treatment and care, prevention of mother-to-child transmission (PMTCT), pre-exposure prophylaxis (PrEP) for pregnant and breastfeeding women, and HIV testing. Other services, including PrEP for anyone else (including those already on PrEP) and HIV prevention more generally, as well as non-clinical programming for orphans and vulnerable children, were not permitted. Even with the waiver, implementers faced challenges in getting permission to resume HIV programming and difficulties getting paid.
  • Dissolution of USAID: USAID was the main government implementing agency for PEPFAR, obligating 60% of its bilateral assistance in FY 2023. Without USAID and most of its staff, PEPFAR’s implementation capacity and operations have been affected. In addition, announcements of reductions at CDC, PEPFAR’s second largest implementing agency (obligating 37% in FY 2023), and questions about the stability of CDC’s funding, could further affect PEPFAR.
  • Canceled awards: In early 2025, it was reported that the administration canceled 86% of all USAID awards. KFF analysis found that of the 770 global health awards identified, 379 included HIV activities, 71% of which were terminated, including several HIV treatment awards as well as most HIV prevention.
  • Legal actions: In response to two lawsuits filed against the administration’s actions, a federal judge issued a preliminary injunction ordering the government to pay for work completed by February 13, 2025, although not all payments have been made and the court did not stop the government from canceling awards. The government appealed the ruling, and after several subsequent rulings in the case, the Supreme Court ultimately allowed the government to rescind (cancel) a portion of expiring global health funds before the end of the fiscal year. Further proceedings have been stayed, pending the outcome of a separate case.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and that any remaining USAID operations would be absorbed by the State Department with global health activities to be integrated into GHSD. On May 29, 2025, the State Department further notified Congress of its proposed reorganization plan, and with the dissolution of USAID, programs moved in July 2025.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. HIV programs are an anchor of the strategy, and HIV has been included in most of the agreements signed to date, although there is little information available on activities and funding. A U.S. Global AIDS Coordinator has yet to be nominated.
  • Long-acting injectable PrEP: On September 4, 2025, the administration announced that PEPFAR would partner with the Global Fund to support provision of long-acting injectable PrEP to up to 2 million people in high-burden countries by 2028.
  • Policy restrictions: In January 2025, the Trump administration reinstated the expanded Mexico City Policy from Trump’s first term and further expanded it in January 2026 to apply to almost all non-military foreign assistance, many more entities, and additional areas of restrictions including activities related to diversity, equity and inclusion and “gender ideology” under a broader umbrella of the “Promoting Human Flourishing in Foreign Assistance” (PHFFA) Policy.
  • Funding: The Trump administration has requested significantly less funding for PEPFAR in its budget requests and canceled funding for numerous HIV-related projects and awards. Despite this, Congress has continued to appropriate funding at or close to prior year levels for PEPFAR, including $4.8 billion in FY 2026. It also appropriated $1.25 billion for the Global Fund in FY 2026.

Impact on PEPFAR Services and Outcomes

Numerous reports have documented the impacts of these actions on services and outcomes:

  • An analysis conducted shortly after the stop-work order was issued found that many PEPFAR implementing partners reported the cancellation of at least one category of activities; staff reductions; and risks to operations. 
  • A rapid assessment survey of 108 WHO country offices, conducted in 2025, found that almost half reported moderate or severe disruptions to HIV services, including for medicines and health products, due to the U.S. foreign aid freeze and other shortages.
  • A recent analysis in 14 countries found that the disruption in PEPFAR funding was associated with significant drops in access from early 2025 through early 2026 and that recovery remains limited, with ongoing reduced access to HIV services and commodities, including antiretroviral treatment, PrEP, HIV tests, and clinical monitoring tests.
  • A tracking survey found that PrEP initiations declined by 13% and 66% in five high-burden countries between January-September 2024 and January-September 2025.
  • A summary of available data as of December 2025 found that while some recovery had been reported in service uptake for HIV testing and treatment services, funding cuts and disruptions were continuing to have negative consequences for coverage of PrEP and other HIV prevention services, programs for adolescent girls and young women, and community-led HIV responses.
  • In addition, several modeling studies have estimated that cuts in or termination of U.S. HIV funding could result in significant increases in new HIV infections and HIV-related deaths over the coming years.
  • A recent analysis surveyed almost 170 PEPFAR-funded organizations in 46 countries, finding that more than 1,700 HIV service sites “closed entirely after terminated or delayed PEPFAR payments” since funding cuts in 2025 and that among organizations that lost funding almost none were able to find alternative funding support. It also found a range of HIV services, including those directed at key populations, HIV prevention such as PrEP and condom distribution, and PMTCT, were stopped, interrupted, or disrupted.
  • A KFF analysis of the latest PEPFAR data provides a snapshot of PEPFAR results after the Trump administration’s changes: For some indicators, progress declined in FY 2025 Q4, including support for prevention services such as PrEP and the DREAMS program for adolescent girls and young women, both of which were significantly scaled back by the administration. There was also a drop in the number of people with HIV newly enrolled on antiretroviral therapy (ART), an important measure of access. There were areas where progress has been maintained or potentially improved, including the total number of people with HIV on ART, which was stable, and an increase in the number of people living with both HIV and TB who are receiving ART.

What to Watch

  • Implementation of the America First Global Health Strategy multi-year agreements with countries
  • Status of U.S. funding appropriated by Congress for PEPFAR and contributions to the Global Fund
  • Impact of the PHFFA Policy on U.S. funding and programs
  • Impact of U.S. changes to global health programs on health outcomes
  • The future of transparent PEPFAR data monitoring and reporting

The Trump Administration’s Foreign Aid Review: Reorganization of U.S. Global Health Programs

Published: Aug 6, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on U.S. Global Health Programs

  • Historically, U.S. global health programs have been overseen and managed by three main federal departments and agencies: the State Department, USAID (now dissolved), and CDC.
    • The State Department is home to the Bureau of Global Health Security and Diplomacy (GHSD), which leads and oversees PEPFAR (which receives direct appropriations from Congress) as well as global health security and, more recently, other global health programs.
    • USAID, an independent agency established by Congress, had housed and managed most other U.S. bilateral global health programs (before its dissolution in 2025), including TB, malaria, maternal and child health, and nutrition, receiving direct appropriations from Congress for these efforts. Because the State Department had not historically served as an implementing agency, USAID also managed more than half of PEPFAR’s funding, through State Department transfers and direct appropriations from Congress.
    • CDC has global programs for HIV, TB, polio, and global health security, which receive direct Congressional appropriations and also manages and implements PEPFAR funding transferred by State and USAID.
  • To carry out global health programs, federal agencies had funded other organizations, including non-profits, foreign governments, and international and multilateral health organizations, such as the Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund) and Gavi, the Vaccine Alliance.
  • Prior to the start of the Trump administration, U.S. funding for global health, across multiple federal agencies and for bilateral and multilateral programs, including global health research, had totaled $12.0 billion in FY 2025.

Current Status of U.S. Global Health Programs

The following administration actions have or are likely to have a significant impact on the structure and operations of U.S global health programs:

  • Stop-work order: The stop-work order, as part of the foreign aid review, initially froze all bilateral global health programming and services, halting existing work in the field (it was not applied to the Global Fund or Gavi). Because it halted payments, many implementers had to terminate staff and end some services.
  • Limited waivers: Certain bilateral global health programs received waivers to allow “life-saving services” to continue, including a limited set of PEPFAR services and TB, malaria, maternal and child health, nutrition and infectious disease outbreak response services. Even with these waivers, services remained disrupted, and implementers faced challenges in getting permission to resume programming and difficulties in getting paid.
  • Dissolution of USAID: Because USAID was the main implementing agency for global health efforts, its dissolution and loss of most of its staff reduced program implementation capacity and operations. Announcements of reductions at CDC could further affect global health efforts.
  • Cancelled awards: In early 2025, it was reported that the administration canceled 86% of USAID awards. KFF analysis found that of the 770 global health awards identified, 80% were listed as terminated, totaling $12.7 billion in unobligated funding.
  • Other executive orders and actions: In addition to the foreign aid review, several other orders and actions have or will likely affect global health, including: a review of international organization participation, the reinstatement and further expansion of the Mexico City Policy (now under a broader umbrella called the Promoting Human Flourishing in Foreign Assistance (PHFFA) Policy) and withholding of UNFPA funding, and withdrawal from the World Health Organization.
  • Legal actions: In response to two lawsuits filed against the administration’s actions, a federal judge issued a preliminary injunction ordering the government to pay for work completed by February 13, 2025, although not all payments have been made and the court did not stop the government from canceling awards. The government appealed the ruling, and after several subsequent rulings in the case, the Supreme Court ultimately allowed the government to rescind (cancel) a portion of expiring global health funds before the end of the fiscal year. Further proceedings have been stayed, pending the outcome of a separate case.
  • Reorganization: The administration moved to restructure and/or reduce global health efforts as follows:
    • On March 28, 2025, Secretary of State Rubio announced that the State Department and USAID had notified Congress of their intent to “restructure certain Department bureaus and offices that would implement programs and functions realigned from USAID” as follows:
      • Proposing legislation to abolish USAID as an independent agency.
      • Separating almost all USAID personnel from federal service within the current fiscal year.
      • Identifying USAID programs that “continue to advance the Administration’s foreign policy objectives,” including a subset of global health activities to be transferred to GHSD. These include programs that help reduce health disparities, deliver lifesaving vaccines, promote maternal and child health, and control malaria, TB, and other diseases.
    • On April 22, 2025, Secretary Rubio announced a reorganization of the State Department to “empower the Department from the ground up, from the bureaus to the embassies”, including removing redundant offices and non-statutory programs that are “misaligned with America’s core national interests.” On May 29, 2025, the State Department notified Congress with further details, including that GHSD would be reorganized to include three major divisions: Health Programs (with the Office of Health Programs and the Office of Program Transition and Supply Chain), Health Policy and Diplomacy (with the Office of Health Diplomacy and the Office of Program Planning and Evaluation), and Global Health Security (with the Office of Outbreak Detection and Response). With the dissolution of USAID in July 2025, U.S. global health programs were moved to the State Department.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement, with 3 broad pillars – making America safer, stronger, and more prosperous – and focusing on HIV, TB, malaria, polio, and global health security. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance. The agreements include co-investment by countries and aim to transition the majority of countries to full self-reliance by the end of the agreement period. The U.S. will provide 100% of current levels of funding for health commodities and frontline healthcare workers for HIV, TB, malaria, and polio through FY 2026 and reduced funding thereafter (and rapidly reduce funding for activities other than health commodities and frontline health personnel). Global health security activities focus on surveillance, data sharing and laboratory capacity, to enable early detection and rapid containment of outbreaks originating outside the U.S. A KFF analysis of the MOUs finds that the administration plans to reduce funding to countries by billions over the next five years, relative to the prior five-year period.
  • Funding: While the Trump administration has requested significantly less funding for global health in its budget requests, Congress has continued to appropriate funding at close to prior year levels, including $11.3 billion in FY 2026.

What to Watch

  • Implementation of the America First Global Health Strategy bilateral, multi-year agreements with selected countries (see KFF tracker)
  • Status of U.S. funding appropriated by Congress for global health programs
  • Impact of the new policies on U.S. funding and programs, including the PHFFA Policy
  • Impact of U.S. changes to global health programs on health outcomes

The Trump Administration’s Foreign Aid Review: Status of U.S. Support for the Global Fund to Fight AIDS, Tuberculosis and Malaria

Published: Aug 6, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. . Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on the U.S. and the Global Fund

  • The Global Fund to Fight AIDS, Tuberculosis and Malaria (Global Fund) is an independent public-private, multilateral financing entity created in 2002. It raises and pools resources from multiple donors to address HIV, TB, and malaria and in turn, invests up to $5 billion per year in more than 100 low- and middle-income countries.
  • The Global Fund reports that it has helped to save 70 million lives and reduce the combined death rate of its three focus diseases by 63% since 2002. With its support, in 2024, 25.6 million people were on antiretroviral therapy, 7.4 million were treated for TB, and 162 million mosquito nets were distributed.
  • The U.S. government was instrumental in the creation of the Global Fund and is its largest donor, accounting for 33% of its funding. It also plays a significant role in governance and oversight of the Global Fund, holding one of twenty Board seats and currently sitting on two Board committees.
  • Only LMICs whose most recent Gross National Income (GNI) per capita is below a certain threshold and meet disease burden criteria are eligible for Global Fund assistance. Countries are required to co-finance by investing in health systems and HIV, TB, and malaria national responses. To date, 11 countries have graduated from Global Fund support.
  • The Global Fund has been considered the “multilateral component” of PEPFAR, as well as U.S. bilateral efforts focused on malaria and TB, complementing and extending the reach of U.S. programs to many more countries. It also works differently than U.S. bilateral health programs; unlike the U.S., it has no in-country presence and does not implement programs, instead providing financial assistance based on technical evaluations of country-led proposals. It also plays an important market shaping role through pooled procurement, driving down prices of health products, accelerating innovation and adoption of new products, and promoting quality standards, among other strategies.
  • U.S. participation in the Global Fund is authorized in the legislation that created PEPFAR, as a permanent part of U.S. law. Other parts of the authorization are time-bound, including several related to the Global Fund such as a requirement that U.S. contributions to the Global Fund cannot exceed 33% of all contributions, used to limit U.S. funding and leverage support from other donors. Because PEPFAR’s current authorization expired on March 25, 2025, this requirement is not in place unless Congress includes it in appropriations or other legislative language.
  • The Global Fund replenishes funding every three years, with periodic “pledging conferences” (the latest was held in November 2025). Its current replenishment (its eighth) generated $12.68 billion in pledges for the 2026-2028 period, including a pledge of $4.6 billion from the U.S.
  • Prior to the start of the Trump administration, U.S. funding for the Global Fund in FY 2024 was $1.65 billion.

Current Status of U.S. Support for the Global Fund

  • Stop-work order: The foreign aid review’s stop-work order initially froze all U.S. bilateral programming but was not applied to the Global Fund or other multilateral institutions. The administration subsequently announced that it canceled 86% of all USAID awards. Since the Global Fund relies on PEPFAR and other U.S. implementers, as well as U.S. government staff and expertise, to assist countries in delivering services, the disruption of that work affected some Global Fund efforts as well.
  • International organizations review: A second executive order, calling for a 180-day review of U.S. participation in all international intergovernmental organizations, was initiated. Per the order, the purpose of the review was to determine which are “contrary to the interests of the United States and whether such organizations, conventions, or treaties can be reformed”. The Global Fund was not on the list of 66 international organizations from which the U.S. withdrew, per a January 7, 2026, presidential memorandum.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. The U.S. government reports that it is coordinating with the Global Fund as it develops these agreements.
  • Long-acting injectable PrEP: On September 4, 2025, the administration announced that PEPFAR would partner with the Global Fund to support provision of long-acting injectable pre-exposure prophylaxis (PrEP) to up to 2 million people in high-burden countries by 2028.
  • Policy restrictions: In January 2025, the Trump administration reinstated the expanded Mexico City Policy from Trump’s first term and further expanded it in January 2026 to apply to almost all non-military foreign assistance, many more entities including multilateral organizations, and additional areas of restrictions including activities related to diversity, equity and inclusion and “gender ideology” under a broader umbrella known as the “Promoting Human Flourishing in Foreign Assistance” (PHFFA) Policy.
  • Funding: The Trump administration has requested significantly less funding for the Global Fund in its budget requests, and has not provided to the Global Fund all of the funding pledged by the U.S. to, and appropriated for, the seventh replenishment period (which included 2025). Despite this, Congress has continued to appropriate funding in support of U.S. pledges, including $1.25 billion in FY 2026. In addition, Congress included language in the FY 2026 spending bill stating that there remained “sufficient unobligated balances” from prior acts “to fulfill the United States pledge for the seventh replenishment.”

What to Watch

  • Implementation of the America First Global Health Strategy multi-year agreements with countries
  • Status of U.S. funding appropriated by Congress for the Global Fund
  • Impact of the PHFFA Policy on U.S. funding and programs, including support for multilateral organizations
  • Impact of U.S. changes to global health programs on health outcomes

The Trump Administration’s Foreign Aid Review: Status of U.S. Support for CEPI

Published: Aug 6, 2026

Editorial Note: Originally published in July 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on the U.S. and CEPI

  • The Coalition for Epidemic Preparedness Innovations (CEPI) aims to accelerate the development of vaccines and other technologies to prepare for and respond to epidemic and pandemic threats. Pooling and leveraging contributions from more than 30 governments, philanthropic foundations, and private sector partners, CEPI invests to drive research and development into vaccine and therapeutic candidates against high-threat pathogens. It also works to strengthen global laboratory and vaccine manufacturer networks and regulatory environments and to research and support vaccine safety. A core focus is its “100 Days Mission”, an effort to reduce the time it takes to develop vaccines and other countermeasures during outbreaks with pandemic potential.
  • Since its founding in 2017, CEPI contributed to the first licensed vaccine for Chikungunya; is supporting the development of vaccines for Lassa fever, MERS, Nipah virus and Rift Valley fever, all of them currently in clinical trials; and aided in the development of seven COVID-19 vaccines that were licensed for use.
  • The U.S. government made its first financial contribution to CEPI in 2020 and has thus far invested $217 million in the organization. It has also collaborated in other ways with the CEPI including through partnerships with U.S. International Development Finance Corporation (DFC), the Department of Defense, and the U.S. Biomedical Advanced Research and Development Agency (BARDA). The U.S. FDA had also been a member of CEPI’s Joint Coordination Group, and USAID, which had managed the relationship with CEPI, before its dissolution in 2025, had held the U.S. government seat on the CEPI Investors Council.
  • CEPI reports that it has contributed significantly to the U.S. economy through its funding of U.S.-based vaccine developers and that this funding far exceeds the amount of funding it has received from the U.S. government.
  • CEPI replenishes funding every five years. For the last replenishment round, held in 2022, the U.S. pledged $150 million over five years, which has been exceeded. The next replenishment round, known as CEPI 3.0, covers the 2027-2031 period. Additionally, CEPI has launched a Ebola R&D funding appeal (specifically medical countermeasures to the Bundibugyo strain of Ebolavirus), to which the U.S. has pledged $50 million. The U.S. accounts for approximately 6% of total contributions received by CEPI to date.
  • Prior to the start of the Trump administration, U.S. funding provided to CEPI in FY 2024 was $100 million.

Current Status of U.S. Support for CEPI

  • Stop-work order: The foreign aid review’s stop-work order initially froze all U.S. bilateral programming but was not applied to CEPI or other multilateral institutions. The administration subsequently announced that it canceled 86% of all USAID awards. KFF analysis found that of 770 global health awards identified, 80% were listed as terminated, including the CEPI contract. CEPI reported that it has not received a termination notice, but it has not received any regular funding from the Trump administration.
  • International organizations review: A second executive order, calling for a 180-day review of U.S. participation in all international intergovernmental organizations, was initiated. Per the order, the purpose of the review was to determine which are “contrary to the interests of the United States and whether such organizations, conventions, or treaties can be reformed”. CEPI was not on the list of 66 international organizations from which the U.S. withdrew, per a January 7, 2026, presidential memorandum.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and that any remaining USAID operations would be absorbed by the State Department, including global health activities, which would be integrated into its Bureau of Global Health Security and Diplomacy (GHSD). On May 29, 2025, the State Department further notified Congress of its proposed reorganization plan. With the dissolution of USAID, programs moved in July 2025.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. Global health security figures prominently in the new strategy, although CEPI, and other international organizations that focus on pandemic preparedness and response, are not mentioned.
  • Funding: The Trump administration has not included funding for CEPI in its budget requests and has provided no regular funding to the organization. Despite this, the Congress has continued to appropriate funding for CEPI, stating that funding should be consistent with prior year amounts.

What to Watch

  • Implementation of the America First Global Health Strategy
  • Status of U.S. regular funding appropriated by Congress for CEPI but, as yet, not provided by the Trump administration
  • Further results of the administration’s international organizations review
  • U.S. international engagement in pandemic preparedness and response

The Trump Administration’s Foreign Aid Review: Status of U.S. Family Planning and Reproductive Health Efforts

Published: Aug 6, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on U.S. Global Family Planning & Reproductive Health (FP/RH) Efforts

  • The U.S. government had supported FP/RH efforts for 60 years and was the largest donor to the sector. It also was one of the largest purchasers and distributors of contraceptives internationally.
  • Still, each year, about 260,000 women die from complications during pregnancy and childbirth, almost all in low- and middle-income countries. Almost one-third of these deaths could be prevented with greater access to contraception. Worldwide, an estimated 259 million women have an unmet need for modern contraception.
  • Recent decades have seen major gains in access to family planning and reproductive health services. The U.S. government contributed significantly to this progress, reporting that in the countries it supported, modern contraceptive prevalence increased from less than 10% in 1965 to 34% in 2023 and family size fell from more than 6 to 3.9. It also estimated that it would reach up to 24 million women and couples with contraceptive services and supplies, helping to prevent 14,000 maternal deaths and 8.1 million unintended pregnancies, in 2023.
  • Prior to its dissolution in 2025, USAID had served as the lead U.S. implementing agency for FP/RH activities, working in 41 countries, with focused efforts in 29 high-need countries and the Francophone West African region. The CDC also supported some global FP/RH activities primarily through research, surveillance and technical assistance.
  • The U.S. role in global FP/RH has often been contested, influenced by differing views and political debates primarily related to abortion. As a result, U.S. foreign assistance funding is governed by several legislative and policy requirements, including the Mexico City Policy (which has been implemented and rescinded along Presidential party lines and was significantly expanded by both Trump administrations), the Helms Amendment, and the Kemp-Kasten Amendment.
  • Prior to the start of the Trump administration, U.S. funding provided to bilateral FP activities in FY 2024 was $575 million; funding for UNFPA was $30.5 million.

Current Status of U.S. FP/RH Programs

The following administration actions have had a significant impact on FP/RH program operations:

  • Stop-work order: The stop-work order initially froze all FP/RH programming and services, halting USAID’s FP/RH programming including procurement and delivery of contraceptive commodities. Because the order halted payments, many implementers had to terminate staff and end some services.
  • Limited waiver: While the State Department issued a waiver of the stop-work order allowing certain “life-saving services” to continue, family planning services were specifically prohibited from continuation, including in the blanket humanitarian waiver issued on January 28, 2025, and the limited global health waiver issued on February 4, 2025.
  • Dissolution of USAID: As the main government implementer of FP/RH efforts, the dissolution of USAID and loss of most staff significantly affected FP/RH implementation capacity and operations. In addition, announcements of reductions at CDC could further affect global FP/RH efforts.
  • Canceled awards: In early 2025, it was reported that the administration has canceled 86% of all USAID awards. KFF analysis found that of the 770 global health awards identified, 233 included FP/RH activities, 85% of which were terminated.
  • Legal actions: In response to two lawsuits filed against the administration’s actions, a federal judge issued a preliminary injunction ordering the government to pay for work completed by February 13, 2025, although not all payments have been made and the court did not stop the government from canceling awards. The government appealed the ruling and after several subsequent rulings in the case, the Supreme Court ultimately allowed the government to rescind (cancel) a portion of expiring global health funds before the end of the fiscal year. Further proceedings have been stayed, pending the outcome of a separate case.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and move any remaining USAID operations to the State Department, with global health activities to be integrated into its Bureau of Global Health Security and Diplomacy (GHSD) which oversees PEPFAR. FP/RH programs were not continued.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. FP/RH activities are not included in these agreements.
  • Policy restrictions: In January 2025, the Trump administration reinstated the expanded Mexico City Policy from Trump’s first term and further expanded it in January 2026 to apply to almost all non-military foreign assistance, many more entities, and additional areas of restrictions including activities related to diversity, equity and inclusion and “gender ideology” under a broader umbrella known as the “Promoting Human Flourishing in Foreign Assistance” (PHFFA) Policy. The administration also withdrew from membership in and support of UNFPA on January 7, 2026.
  • Funding: The Trump administration has requested no funding for FP in its budget requests and stopped supporting this work in 2025, including rescinding FP funding and withholding funding from UNFPA. Despite this, Congress has continued to appropriate level funding for these programs including $575 million for bilateral FP activities and $32.5 million for UNFPA in FY 2026.

Impact on FP/RH Services and Outcomes

  • A rapid assessment survey of 108 WHO country offices in 2025 found that more than four in ten reported moderate or severe disruptions to FP and contraception services, with 38% reporting such disruptions for commodities specifically, due to the U.S. foreign aid freeze and other shortages.
  • Reports have indicated that millions of dollars in shipments of already purchased contraceptive commodities intended for low- income countries expired while the administration assessed whether to incinerate the supplies or transfer them to another distributor.
  • It is estimated that the loss of U.S. funding in 2025 resulted in a global contraceptive procurement funding gap of approximately $250 million.
  • In addition, several modeling studies have found that cuts in or termination of U.S. FP funding could result in significant increases in unintended pregnancies, unsafe abortions, and maternal deaths.

What to Watch

  • Implementation of the America First Global Health Strategy multi-year agreements with countries and whether countries will choose to continue any FP activities previously supported by the U.S. government.
  • Status of U.S. funding appropriated by Congress for bilateral FP efforts and contributions to UNFPA
  • Impact of the PHFFA Policy on U.S. funding and programs
  • Impact of U.S. changes to global health programs on health outcomes

The Trump Administration’s Foreign Aid Review: Status of Global Health Security/Pandemic Preparedness

Published: Aug 6, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on U.S. Global Health Security Efforts

  • The U.S. has supported global health security (GHS) and pandemic preparedness efforts for decades through funding and technical support provided to low- and middle-income countries (as well as support for multilateral efforts). This had included the development of formal GHS partnerships with other countries, starting with 17 in 2014 and rising to more than 50 in 2024.
  • GHS efforts are designed to help countries and regions build capacities needed to prevent avoidable outbreaks, detect infectious disease threats early, and reduce the impacts of epidemics and pandemics through rapid and effective responses.
  • Specific activities include: improving surveillance and laboratory systems, reducing the risks of animal to human disease exposures, training epidemiologists, and fostering better biosafety and biosecurity practices.
  • U.S. investments in GHS have led to measurable increases in capacity, including improvement in 9 of 15 technical areas between 2018 and 2023 in GHS partnership countries and reductions in average outbreak response times.
  • Prior to 2025, multiple U.S. agencies, coordinated by the National Security Council (NSC), were involved in these efforts including USAID (now dissolved), the Centers for Disease Control and Prevention (CDC), the Department of Defense (DoD), the State Department, HHS, and USDA. The first U.S. GHS Strategy was released in 2019 by the first Trump administration and an updated strategy was released by the Biden administration in 2024.
  • Prior to the start of the Trump administration, U.S. funding provided to bilateral GHS activities in FY 2024 was $1.25 billion; $100 million was provided to the Coalition for Epidemic Preparedness Innovations (CEPI) and $250 million to the Pandemic Fund.

Current Status of U.S. Global Health Security Programs

The following administration actions have had a significant impact on U.S. GHS programs:

  • Stop-work order: The stop-work order initially froze all USAID-based GHS programming and services. As a result, many GHS implementing partners let staff go and some USAID-supported GHS activities in progress were interrupted, such as funding for transport of samples and phone plans for contact tracers.
  • Limited waiver: Some GHS activities were included in a limited waiver issued by the State Department on February 4 allowing “life-saving services” to continue, including: rapid emergency response to immediate infectious disease outbreaks, focused on pathogens with pandemic potential and those that pose a national security risk to U.S. citizens (e.g., mpox and H5N1), including detection, prevention, and containment and supply of medical countermeasures. Even with the waiver, services remained disrupted and implementers faced challenges in getting permission to resume programming and difficulties in getting paid.
  • Dissolution of USAID: Before its dissolution, USAID had about 50 staff supporting international outbreak response efforts, a number which dropped to six in the early weeks of the Trump administration. As a result, many GHS partners lost points of contact and technical support, in addition to the loss of funding. Announcements of reductions at the CDC could further affect GHS capacity.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and that any remaining USAID operations would be absorbed by the State Department with global health activities (including for GHS) to be integrated into its Bureau of Global Health Security and Diplomacy (GHSD). On May 29, 2025, the State Department further notified Congress of its proposed reorganization plan, and with the dissolution of USAID, programs moved in July 2025.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement (the Trump administration withdrew the 2024 Global Health Security Strategy and has not released an updated strategy). Per the America First strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. Global health security figures prominently in the new strategy and is part of all of the agreements signed to date. Goals include enabling detection of outbreaks with epidemic potential within seven days and containing outbreaks originating outside the U.S. rapidly at their source, prioritizing mobilization within 72 hours of detection.
  • Withdrawal from WHO: In January 2025, President Trump announced that the U.S. would withdraw from the World Health Organization (WHO) and halted its funding (the formal withdrawal was completed in January 2026). The administration also said that the U.S. would not be bound by the recently revised International Health Regulations or the new pandemic agreement being negotiated by WHO, two international instruments that outline roles and responsibilities for countries to prepare for and respond to outbreaks.
  • Funding: The Trump administration has requested significantly less funding for GHS in its budget requests and canceled or suspended funding for GHS-related projects and awards, including for contributions to CEPI and the Pandemic Fund. Despite this, Congress has continued to appropriate funding for bilateral GHS efforts at close to prior year levels, including $1.1 billion in FY 2026, and called for funding consistent with prior amounts for contributions to CEPI and the Pandemic Fund.

Impact on GHS Services and Outcomes

  • The combination of administration actions described above has reduced capacity and may challenge communication and coordination across U.S. agencies and with partners, contributing to slower responses to emerging health threats, greater impacts, and increased risk of importation of diseases into the U.S.
  • Experts estimate that there is a 50% chance of another pandemic emerging in the next 25 years, with the risk greatest in the least prepared countries. 
  • The health impacts of poorly controlled outbreaks can be severe. An internal USAID memo from 2025 estimated that the risk of losing USAID GHS programs alone could result in more than 28,000 new cases of dangerous infectious diseases, such as Ebola and Marburg, every year.
  • Emerging diseases can result in major economic and social costs, even with small-scale outbreaks.
    • The SARS 2003 outbreak led to an estimated $30 billion in economic losses (over $3 million per case) from reduced commerce, travel and trade.
    • The 2014-2015 West Africa Ebola epidemic led to an estimated $53 billion in economic losses. A single Ebola patient in New York cost the city’s $4.3 million in response measures.
    • Measles outbreaks in the U.S., often initiated through importation from other countries, can lead to significant costs; a recent study from Washington state found that a 71-case measles outbreak led to societal costs of $3.4 million, or almost $50,000 per case.
  • Pandemics have even more massive economic costs, as experienced with COVID-19, which cost the U.S. alone an estimated at $16 trillion – a number four times the lost economic output from the 2008 financial crisis.
  • News broke in mid-May of the ongoing Ebola outbreak in the Democratic Republic of the Congo, and given all of the changes made by the U.S. to its foreign assistance and global health response, U.S. support is taking shape under very different circumstances and through different organizational mechanisms than in the past, but a recent KFF analysis found that the speed of the U.S. government’s response to the current outbreak is on par with the prior two outbreaks, and initial U.S. funding amounts are already surpassing the prior two outbreaks.

What to Watch

  • Implementation of the America First Global Health Strategy multi-year agreements with countries
  • Status of U.S. funding appropriated by Congress for bilateral GHS efforts and contributions to CEPI and the Pandemic Fund
  • U.S. international engagement in pandemic preparedness and response

The Trump Administration’s Foreign Aid Review: Status of U.S. Support for Gavi, the Vaccine Alliance

Published: Aug 6, 2026

Editorial Note: Originally published in May 2025, this resource has been updated as new information became available.

Starting on the first day of his second term, President Trump issued several executive actions that have fundamentally changed foreign assistance. These included: an executive order which called for a 90-day review of foreign aid; a subsequent “stop-work order” that froze all payments and services for work already underway; the dissolution of USAID, including the reduction of most staff and contractors; and the cancellation of most foreign assistance awards. Although a waiver to allow life-saving humanitarian assistance was issued, it was limited to certain services only and difficult for program implementers to obtain. Since then, responsibility for remaining global health programs has been transferred to the State Department. While there have been several legal challenges to these actions, there has been limited legal remedy to date. As a result, U.S. global health programs were disrupted and, in some cases, ended. Changes to the Department of Health and Human Services, including proposed cuts and reorganization, are also likely to affect these programs. This fact sheet is part of a series on the status of U.S. global health programs.

Background on the U.S. and Gavi

  • Gavi, the Vaccine Alliance (Gavi), is an independent public-private, multilateral financing entity created in 2000. It raises and pools resources from multiple donors and in turn, disburses approximately $1.7 billion per year to support procurement and distribution of vaccines in low- and middle-income countries (LMICs).
  • Gavi supports vaccines against 20 infectious diseases, and hosts the global emergency vaccine stockpiles against Ebola, yellow fever, meningitis, and cholera. By playing a market shaping role through pooled procurement, demand forecasting, support for regional manufacturing capacity, and other strategies, Gavi helps to drive down prices for vaccines in LMICs.
  • Gavi reports that it has helped to immunize more than 1.2 billion children in 78 LMICs, preventing more than 20 million deaths, and generating economic benefits estimated at more than $280 billion, since 2000.
  • The U.S. government was one of the original donors to Gavi and had been its third largest contributor in recent years, providing 13% of its funding since its inception. Gavi also had a donor liquidity partnership with the U.S. International Development Finance Corporation (DFC) allowing Gavi to quickly access up to $1 billion from a “Rapid Financing Facility” to support routine immunization and pandemic response, backed by forthcoming donor pledges. Additionally, the U.S. was the largest donor to COVAX, the international effort housed at Gavi that supported the development, procurement, and delivery of COVID-19 vaccines to LMICs (COVAX ended in 2023).
  • Only LMICs whose most recent Gross National Income (GNI) per capita is below a certain threshold are eligible for Gavi assistance (56 countries in 2026). Countries are required to co-finance a portion of their vaccines on a sliding scale. To date, 19 countries have graduated from Gavi assistance.
  • Gavi had been the primary mechanism by which the U.S. government supported the procurement of vaccines for LMICs. The USAID bilateral maternal and child health program had complemented Gavi by supporting in-country capacity building and immunization campaigns and, prior to its dissolution in 2025, USAID had managed the U.S. partnership with Gavi.
  • Every five years, Gavi replenishes funding through “pledging conferences”. For the 2026-2030 period, Gavi secured more than $9 billion towards a target budget of $11.9 billion, which it estimates would save at least 8 million lives by 2030.
  • Prior to the start of the Trump administration, U.S. funding provided to Gavi in FY 2024 was $300 million.

Current Status of U.S. Support for Gavi:

  • Stop-work order: The foreign aid review’s stop-work order initially froze all U.S. bilateral programming but was not applied to Gavi or other multilateral institutions. The administration subsequently announced that it canceled 86% of all USAID awards. KFF analysis finds that of 770 global health awards identified, 80% are listed as terminated, including the main Gavi contract as well as the COVAX contract. Gavi reports that it has not received a termination notice for its main contract, although it did receive one for COVAX (all U.S. funding was already disbursed to COVAX in 2021).
  • International organizations review: A second executive order, calling for a 180-day review of U.S. participation in all international intergovernmental organizations, was initiated. Per the order, the purpose of the review was to determine which are “contrary to the interests of the United States and whether such organizations, conventions, or treaties can be reformed”. Gavi was not on the list of 66 international organizations from which the U.S. withdrew, per a January 7, 2026, presidential memorandum.
  • Reorganization: The administration notified Congress on March 28, 2025, of its intent to permanently dissolve USAID and that any remaining USAID operations would be absorbed by the State Department, including global health activities which would be integrated into its Bureau of Global Health Security and Diplomacy (GHSD). Delivery of lifesaving vaccines is listed among the USAID activities to be continued at GHSD, although currently the relationship with Gavi is being managed through the Office of Global Affairs at the Department of Health and Human Services. On May 29, 2025, the State Department further notified Congress of its proposed reorganization plan, and with the dissolution of USAID, programs moved in July 2025.
  • America First Global Health Strategy: In September 2025, the administration released the America First Global Health Strategy, its roadmap for future U.S. government global health engagement. Per the strategy, the U.S. is negotiating bilateral, multi-year agreements with countries receiving U.S. global health assistance with an aim to transition the majority of countries to full self-reliance by the end of the agreement period. While the strategy and country agreements include the importance of polio and malaria vaccination and metrics for measuring their delivery, Gavi is not mentioned, and the U.S. has not announced how it will procure these vaccines.
  • Funding: The Trump administration has not included funding for Gavi in its budget requests, including its FY27 budget request that stated that any future funding for Gavi is “contingent on the organization making necessary reforms and meeting certain benchmarks on vaccine safety.” While Congress appropriated $300 million for U.S. contributions to Gavi in FY 2025 and FY 2026, the current administration has not provided funding to Gavi after citing concerns about vaccine safety, despite Gavi following globally-recognized scientific standards and evidence. Gavi has committed to working toward accelerating its transition to different vaccines, in partnership with its Board and countries, and based on manufacturers ability to expand production capacity, among other factors. On July 29, 2026, the administration announced it would “immediately release” $600 million in Congressionally-appropriated FY25 and FY26 funding to Gavi.
  • U.S. representation on the Gavi Board: The U.S. historically played a role in Gavi’s governance, including as a Board and committee member, but with the suspension of U.S. funding by the Trump administration, the U.S. is no longer eligible to be part of the Board. In its recent announcement that it would resume funding, the administration stated that the U.S. “expects to resume its place on the Gavi Board.”   
  • Potential impact on health outcomes: The loss of U.S. support for Gavi would affect procurement of vaccines for LMICs, with particular impact on children. Gavi estimates that loss of funding could result in 75 million children not receiving routine vaccinations over the next five years, leading to more than 1.2 million children dying as a result. Reductions in vaccine stockpiles could also impact outbreak control.

What to Watch

  • Implementation of the America First Global Health Strategy
  • Status of U.S. funding appropriated by Congress for Gavi and the U.S. role in Gavi governance
  • Further results of the administration’s international organizations review
  • Impact of U.S. changes to global health programs on health outcomes