Total Run Time: 2:09

Total Run Time: 2:09

What Do We Get for the Cut Health Insurers Take?

Narrated by:

Published:

Insurers take a cut of every premium dollar for overhead and profit. The question isn’t just whether they profit, but also whether we’re getting value in return.

KFF’s Larry Levitt breaks down how much goes to administrative costs and profit and how that varies across private insurance markets and Medicare, and considers what a Medicare-for-all system, which would be operated by the government, would address and what might be left unresolved. 


Watch and share the full series. Available on YouTube. 

KFF encourages linking to and reposting of our content on social media and other digital platforms.

Choose a video from our YouTube channel, click the Share button, select Embed, and copy the generated <iframe> code. Paste this HTML code directly into your websites editor or source code.

For collaboration or to request direct video downloads (vertical and horizontal formats) and carousel graphics, email us at outreach@kff.org

Subscribe to the KFF YouTube Channel. Stay connected with KFF on other social platforms. 

When citing us, please note our legal name is KFF. We should be cited as KFF, a nonprofit health policy research, polling, and news organization. Our name is no longer the Kaiser Family Foundation. More about KFF citations and permissions. 

The videos were scripted and produced by KFF. Visuals and graphics were developed using Adobe Creative Cloud with assistance from AI tools and refined by a graphic designer. Additional content: C-SPAN.


Video Transcript

Narrated by Larry Levitt, KFF Executive Vice President for Health Policy

Insurers take a cut of every premium dollar. The question isn’t whether they profit, it’s what value we’re getting in return.

Insurers siphon off premium dollars for overhead and profit, averaging annually $846 per enrollee in the employer market, $987 in the individual insurance market, and $1,655 in Medicare Advantage.

Setting aside administrative costs, profit margins of health insurers are on paper generally modest. Typically, no more than a few percent of premium revenues. But a few percentages of a very large number is still a very large number.

The seven largest publicly-held health insurance companies pulled in an estimated $71 billion in profits in 2024, including subsidiaries, like pharmacy benefit managers.

How that money flows looks different depending on the program.

In Medicare Advantage – the private insurance option now covering over half of beneficiaries – about 90 cents of every premium dollar goes toward health care, while the remaining 10 cents goes to overhead and profit. 

By contrast, less than two cents of every Medicare dollar goes to administering traditional Medicare. And as a public program, there is no profit. 

The difference? Traditional Medicare is administered by the government rather than private insurance companies. 

And in traditional Medicare the government sets prices for hospitals and doctors directly rather than negotiating them through private insurers.

Taking health insurance companies out of the equation – for example, under a Medicare for All system operated by the government – would reduce administrative costs and profits. But the biggest drivers of health spending growth – hospital prices, care that is not always grounded in evidence, and new drugs and medical technologies – would remain and have to be dealt with somehow.

We started by asking what value insurers provide for their cut. But the real question may be, who do we trust to decide what health care gets covered and how much gets paid? 

MORE HEALTH POLICY VIDEOS

Series

Health in the 2026 Midterm Elections

This research is part of KFF’s Health in the Midterms series, a collection of policy research, polling and news from across KFF about election-related health care issues.


CONTACT

Ann DeFabio

Senior Vice President and Chief Communications Officer

annd@kff.org

Total Run Time: 2:07

Total Run Time: 2:07

Who Do We Trust to Decide What Health Care Gets Covered, and at What Price?

Narrated by:

Published:

Deciding what health care gets covered largely falls to health insurers, and it’s not a role that wins them many fans. A KFF poll finds prior authorization is the single biggest burden insured adults say they face beyond cost. 

KFF’s Larry Levitt weighs insurers’ role as a check on care that lacks medical evidence against the impact that delays and denials have on patient care and health care providers. 


Watch and share the full series. Available on YouTube. 

KFF encourages linking to and reposting of our content on social media and other digital platforms.

Choose a video from our YouTube channel, click the Share button, select Embed, and copy the generated <iframe> code. Paste this HTML code directly into your websites editor or source code.

For collaboration or to request direct video downloads (vertical and horizontal formats) and carousel graphics, email us at outreach@kff.org

Subscribe to the KFF YouTube Channel. Stay connected with KFF on other social platforms. 

When citing us, please note our legal name is KFF. We should be cited as KFF, a nonprofit health policy research, polling, and news organization. Our name is no longer the Kaiser Family Foundation. More about KFF citations and permissions. 

The videos were scripted and produced by KFF. Visuals and graphics were developed using Adobe Creative Cloud with assistance from AI tools and refined by a graphic designer. Additional content: C-SPAN.


Video Transcript

Narrated by Larry Levitt, KFF Executive Vice President for Health Policy

Prior authorization keeps health care costs down. And patients often waiting for care.

The job of deciding what health care gets covered largely falls to health insurers, and it’s not a role that wins them many fans.

Costly insurance premiums are straining consumers and employers alike. But those premiums are high mainly because of spending for hospital care, physician services, and prescription drugs.

At almost a third of national health expenditures, hospitals account for the largest share of total spending and also drive more growth than other parts of the health care system. 

Though they may not do it very effectively, insurers are a counterweight to a consolidated hospital industry that uses its market power to charge higher prices. 

The prices paid by private insurers for hospital care are about double what Medicare pays and have risen much faster too. Up 30% for private insurers versus 21% for Medicare.

Insurers have limited tools to control prices. Prior authorization is their main lever on volume. 

Insurers see it as pushing back against a system that incentivizes doing more rather than less, discouraging care that is not medically necessary. But patients and clinicians experience it as insurers saying no to care they believe is needed.

A KFF survey of insured adults found that prior authorization was the single biggest health care burden beyond costs.

When insurers push back on requests, some services don’t happen and even the possibility of a denial changes how clinicians practice. They order less, knowing some requests won’t be approved.

Nearly half of insured adults said they’d had care denied or delayed in the two years prior, with many reporting consequences for their physical health, emotional well-being, or finances.

Insurers may be imperfect referees, but some entity has to address what health care needs to be covered and at what price. The question is who do we trust to make those calls most effectively and fairly?

MORE HEALTH POLICY VIDEOS

Series

Health in the 2026 Midterm Elections

This research is part of KFF’s Health in the Midterms series, a collection of policy research, polling and news from across KFF about election-related health care issues.


CONTACT

Ann DeFabio

Senior Vice President and Chief Communications Officer

annd@kff.org

Tracking Implementation of the 2025 Reconciliation Law: Medicaid Work Requirements

Updated on:

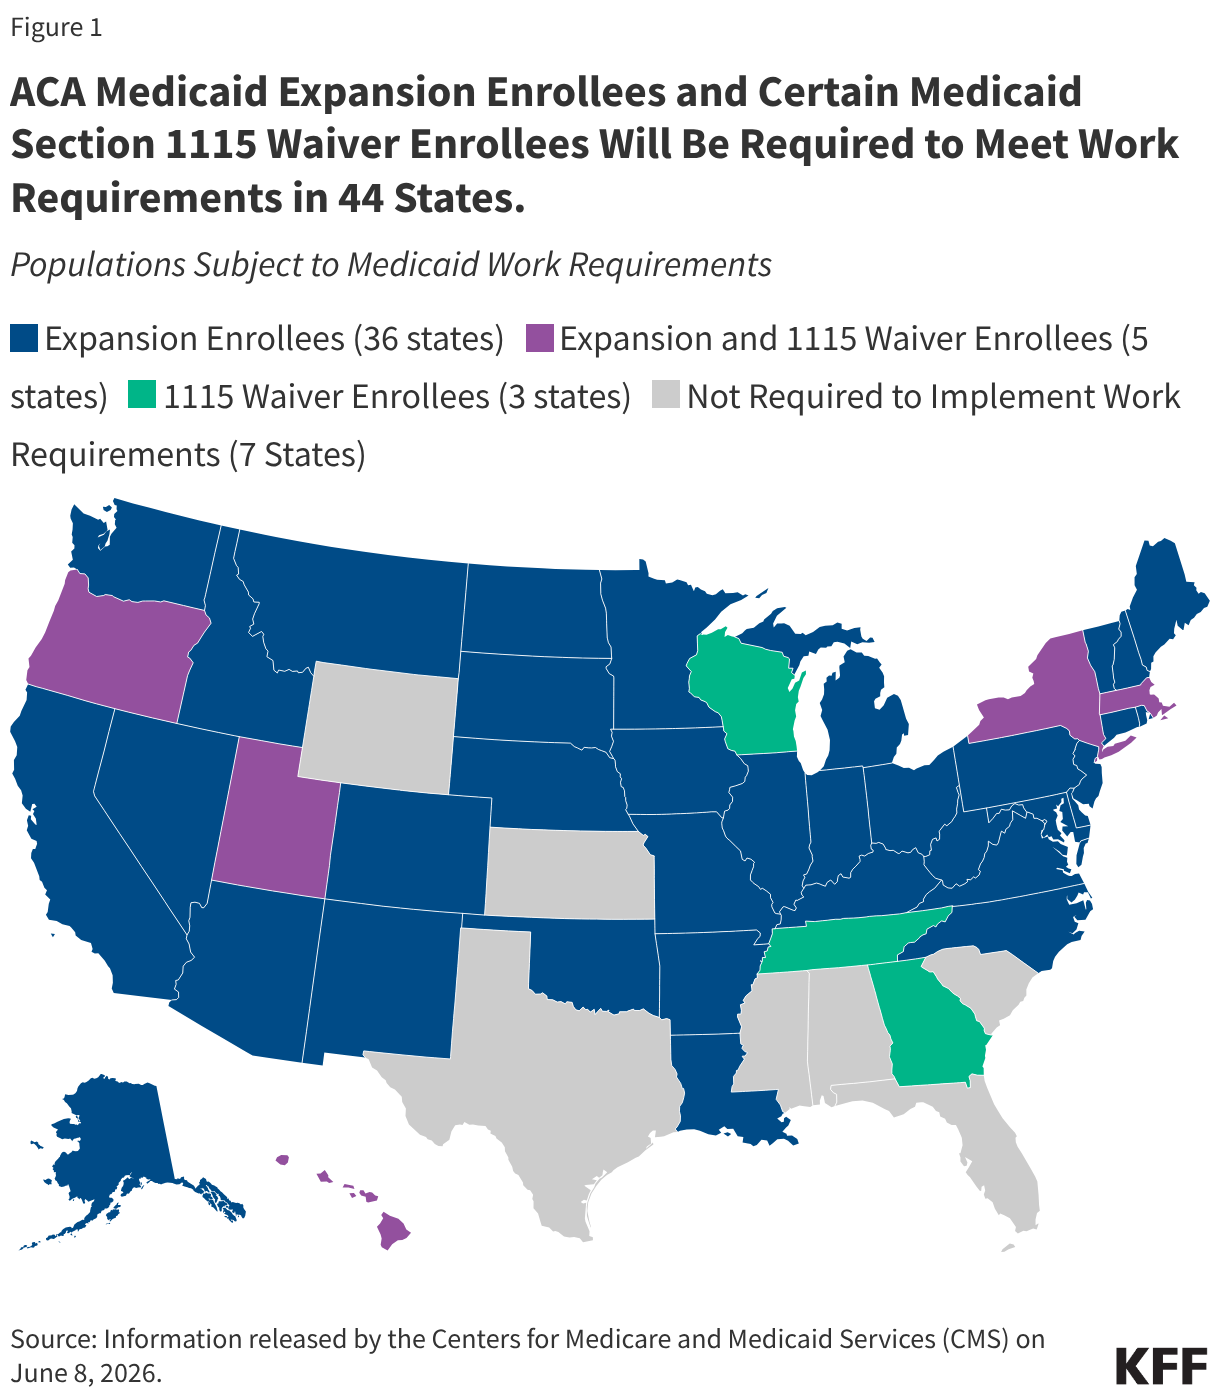
The 2025 reconciliation law, once called the “One Big Beautiful Bill,” signed by President Trump on July 4, 2025, requires 44 states (including DC) to condition Medicaid eligibility for adults in the Affordable Care Act (ACA) Medicaid expansion group and certain enrollees in 1115 waiver programs on meeting work requirements starting January 1, 2027. Currently, 41 states (including DC) have expanded their Medicaid programs under the ACA to nearly all adults with income up to 138% FPL ($21,597 for an individual in 2025). In June 2026, CMS released a list of states with 1115 waiver programs that include individuals who will be subject to work requirements. The list identifies waiver programs in three non-expansion states Georgia, Tennessee, and Wisconsin, as well as in five expansion states, Hawaii, Massachusetts, New York, Oregon, and Utah (Figure 1).  

ACA Medicaid Expansion Enrollees and Certain Medicaid Section 1115 Waiver Enrollees Will Be Required to Meet Work Requirements in 44 States. (Choropleth map)

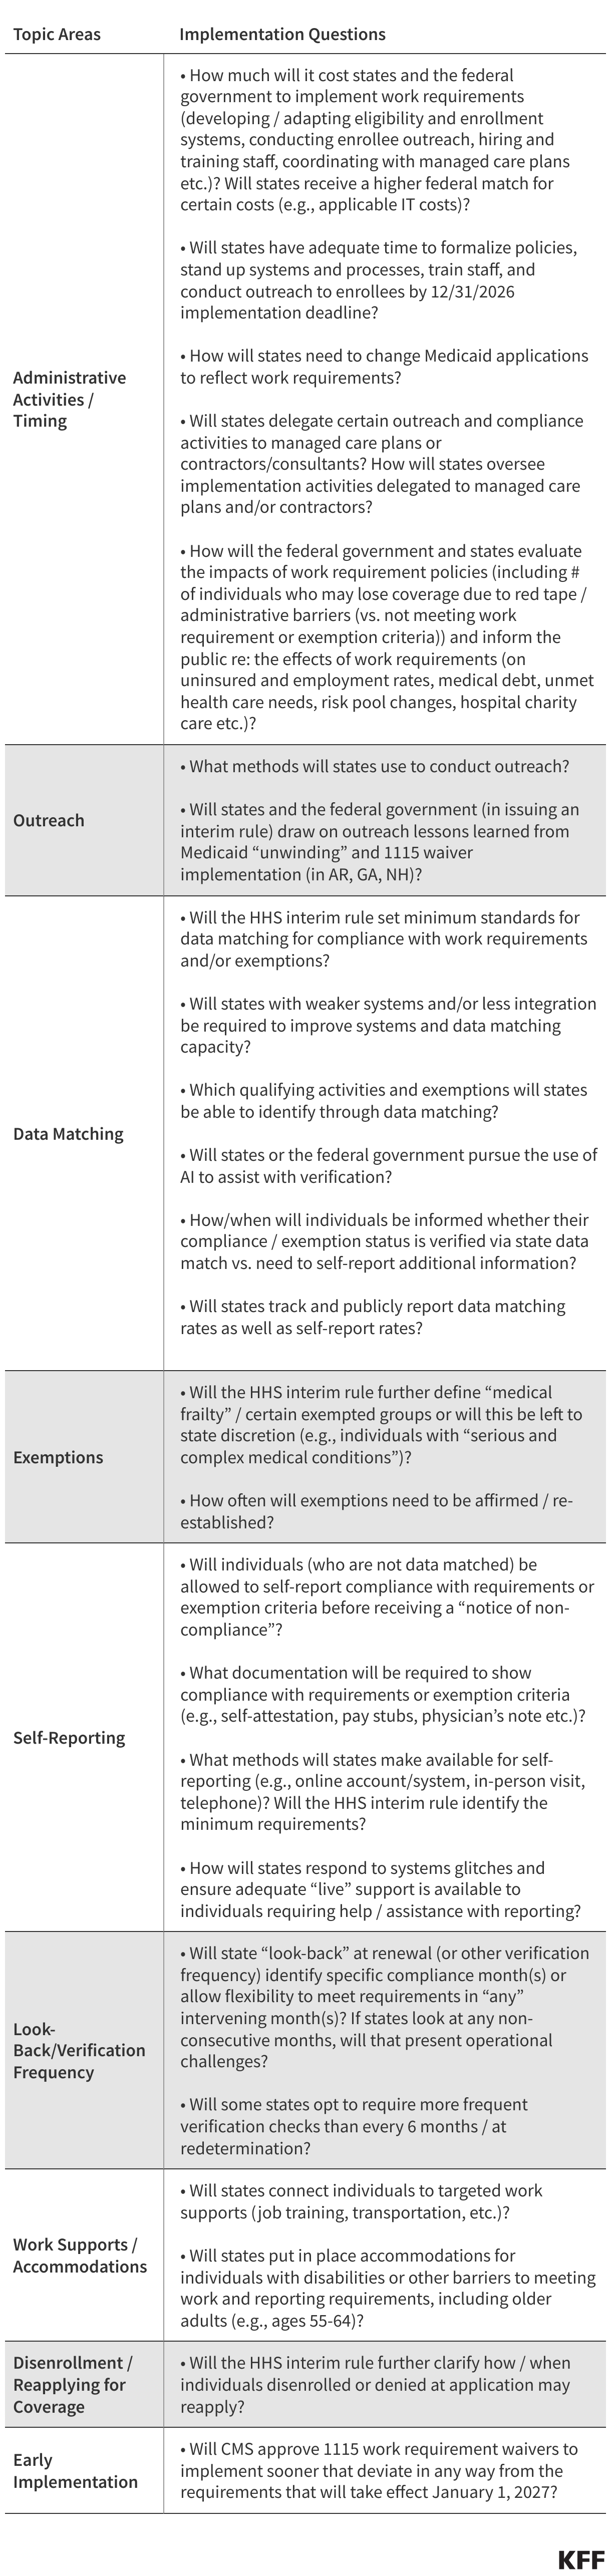
To implement Medicaid work requirements, states will need to make important policy and operational decisions, implement needed system upgrades or changes, develop new outreach and education strategies, and hire and train staff, all within a relatively short timeframe. The information tracked here can serve as a resource to understand Medicaid work requirements and state options, gauge readiness, and track implementation of the requirements, including:

This resource will be updated to include guidance from the Centers for Medicare and Medicaid Services (CMS), information on state policy decisions as they are made, and new data when available.

Continue scrolling to learn more about the Medicaid work requirements in the 2025 reconciliation law.

Tracking Implementation of the 2025 Reconciliation Law Medicaid Work Requirements

Updated on:

CMS Guidance and Information

Operational and Implementation Questions

Table

Tracking Implementation of the 2025 Reconciliation Law Medicaid Work Requirements

Updated on:

The 2025 reconciliation law requires states to condition Medicaid eligibility for adults in the ACA Medicaid expansion group on meeting work requirements starting January 1, 2027; however, states have the option to implement requirements sooner through a state plan amendment (SPA) or through an approved 1115 waiver.

State Plan Amendments (SPAs)

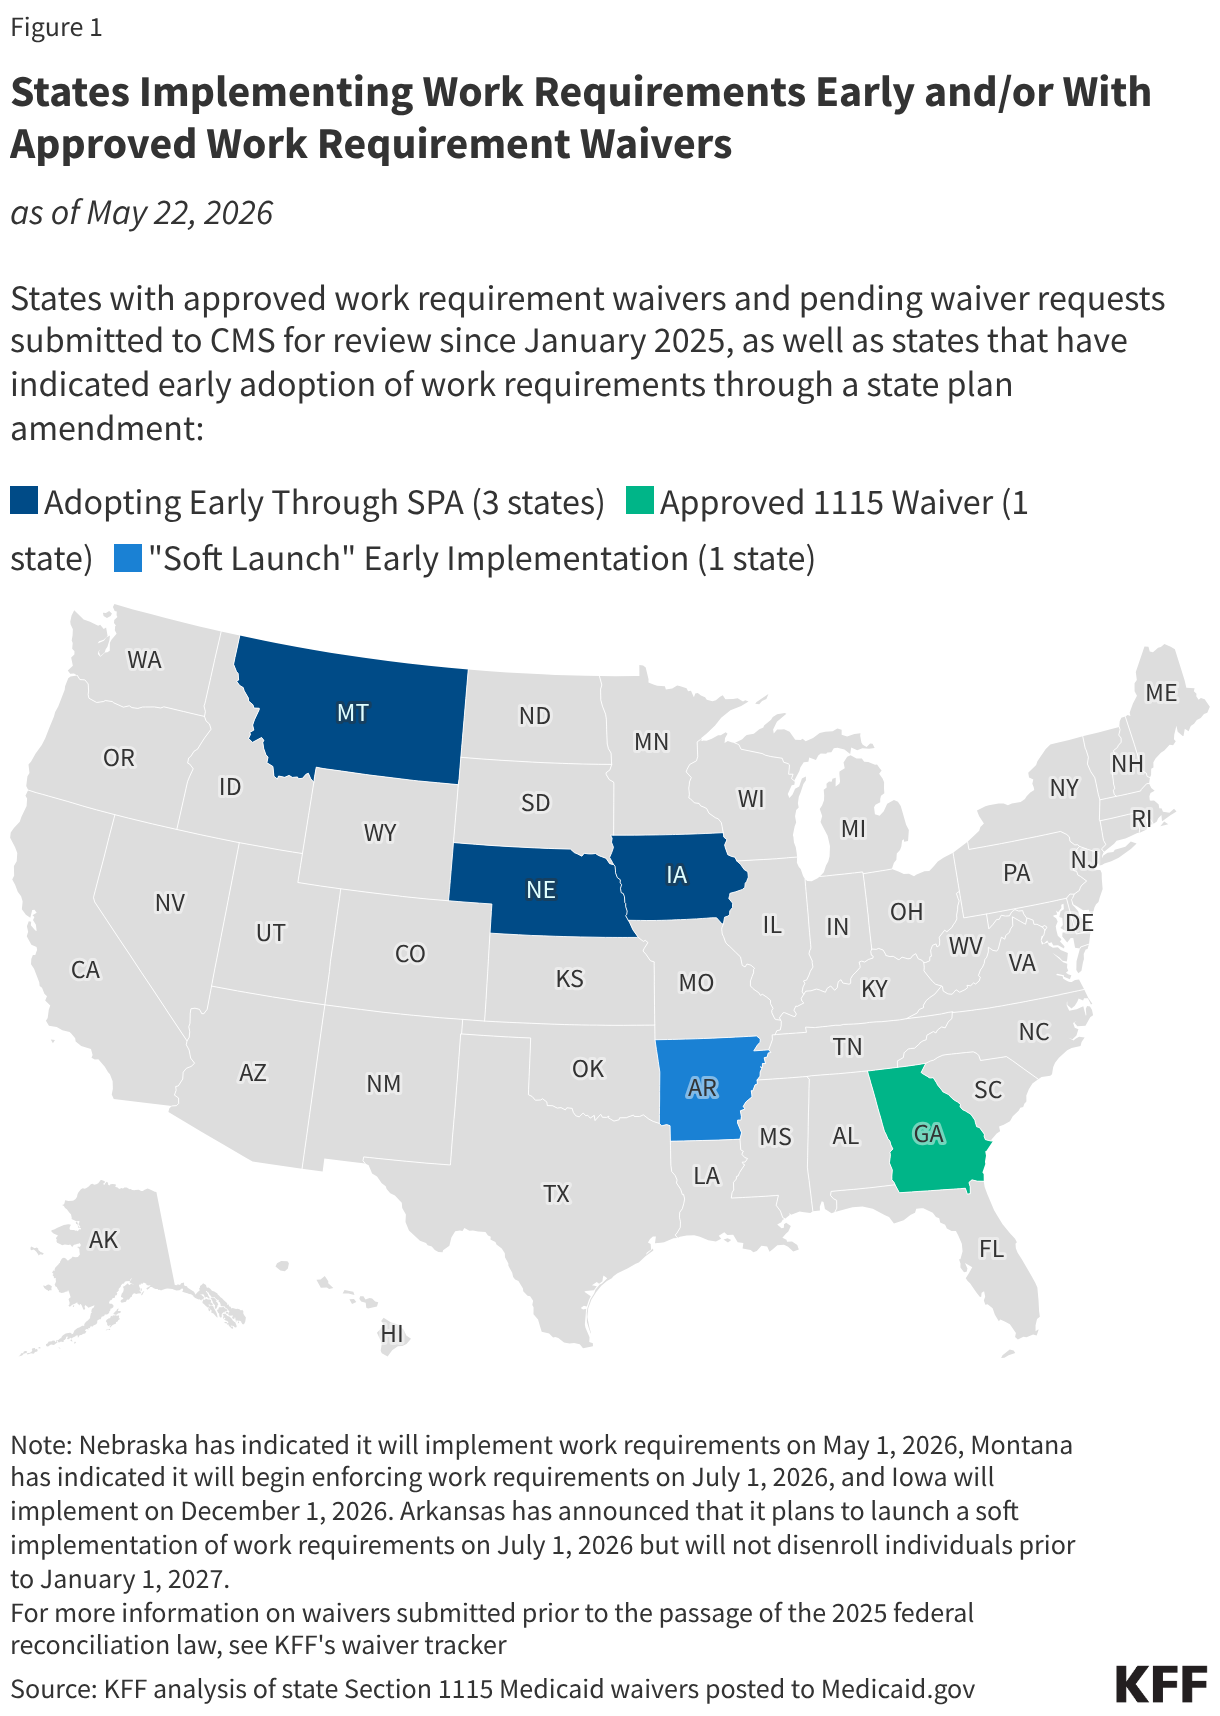
States may choose to implement work requirements prior to the required January 1, 2027 implementation date through a state plan amendment. Nebraska is the first state to announce that it will begin enforcing federal work requirements early through a state plan amendment, starting May 1, 2026. Two other states are also planning to implement before January 2027–Montana on July 1, 2026 and Iowa on December 1, 2026. Arkansas has announced that it plans to launch a soft implementation of work requirements on July 1, 2026 but will not disenroll individuals prior to January 1, 2027.

1115 Waivers

Since the start of the second Trump administration, several states have submitted waivers to implement work requirements. However, states are unlikely to be moving forward with proposed 1115 waivers at this time due to the passage of federal work requirements. States that plan to implement federal work requirements early will do so through a state plan amendment. Currently, Georgia is the only state with a Medicaid work requirement waiver in place following litigation over the Biden administration’s attempt to stop it. Georgia’s waiver will expire December 31, 2026; the state is required to come into compliance with the new federal requirements effective January 1, 2027.

Early Implementation and Waiver Status

The map below identifies states that have indicated they will implement federal work requirements early through a state plan amendment and the one state (Georgia) that has implemented work requirements through an 1115 waiver.

States Implementing Work Requirements Early and/or With Approved Work Requirement Waivers (Choropleth map)

Tracking Implementation of the 2025 Reconciliation Law Medicaid Work Requirements

Updated on:

KFF Resources on Medicaid Work Requirements

Work requirements overview:

Medical frailty exemption:

Implementation of work requirements:

50-state survey of Medicaid eligibility and enrollment policies:

Research and analysis on Medicaid and work:

1115 work requirement waivers:

Work requirements implications and state experience:

Arkansas work requirement experience:

KFF Polling on Work Requirements:

Beyond the Data by KFF CEO Drew Altman:

Medicaid/CHIP Monthly Enrollment Tracker

Published: Sep 8, 2026

Note: The data presented below are updated monthly as new Medicaid/CHIP enrollment data become available.

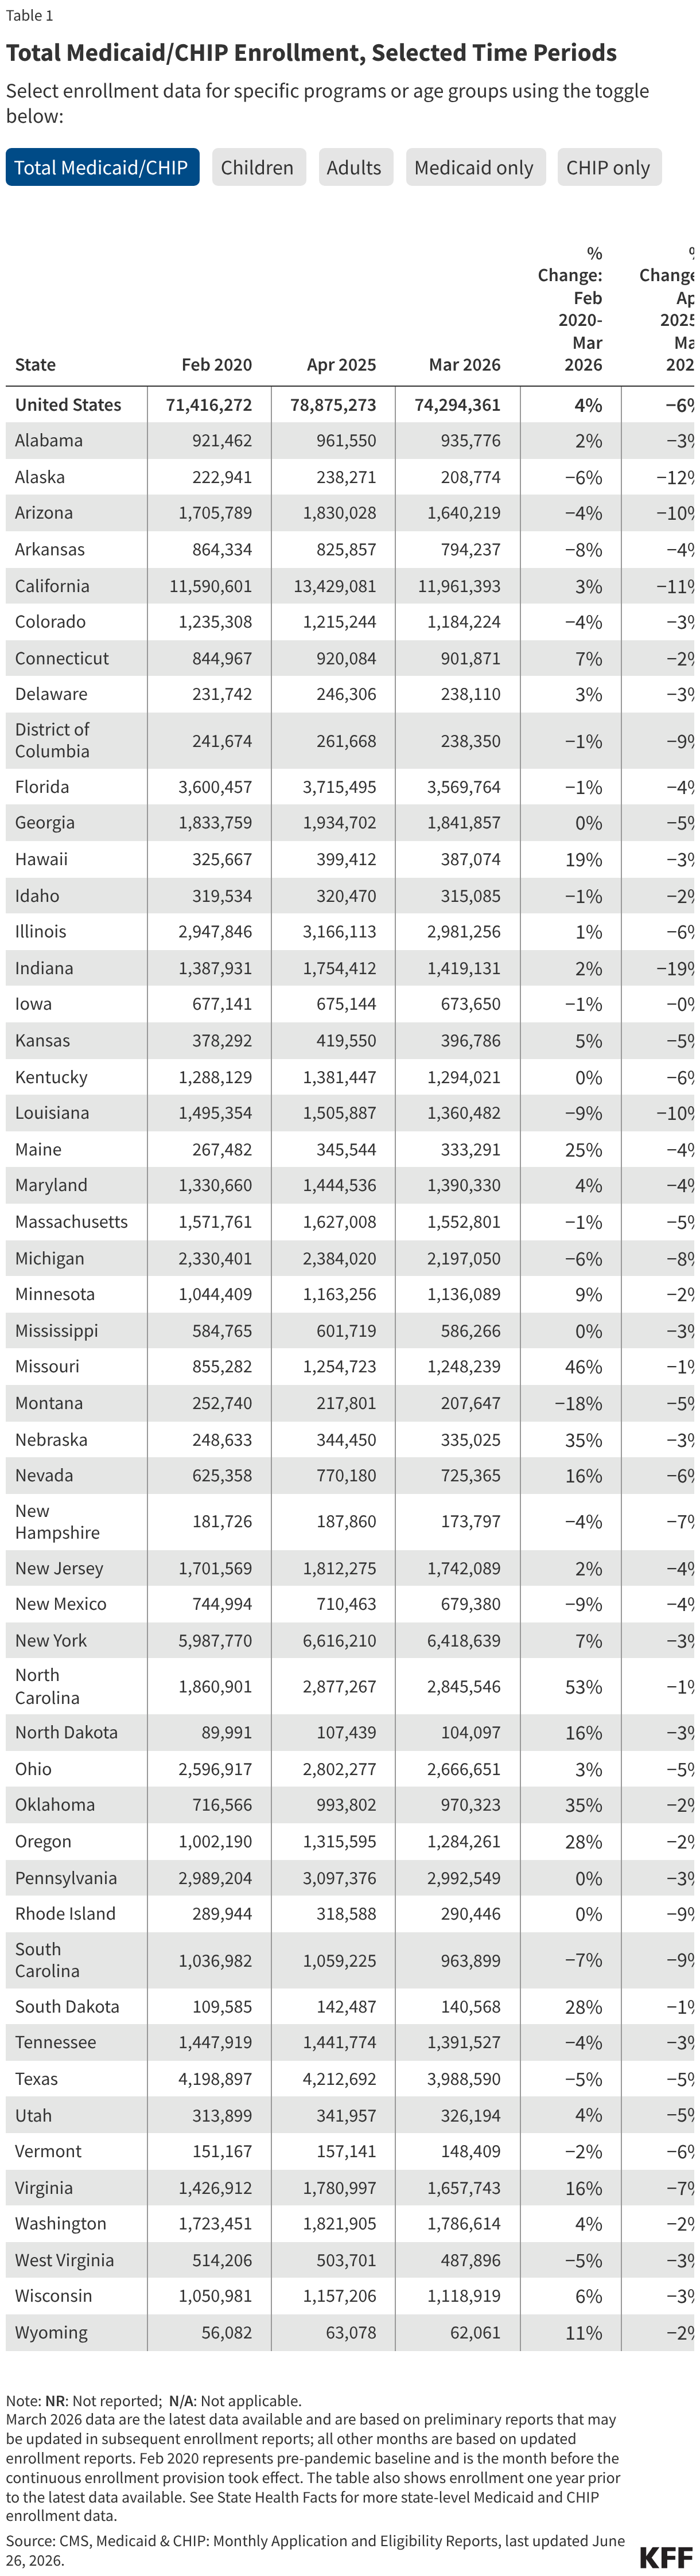
This tracker presents the most recent data on monthly Medicaid and Children’s Health Insurance Program (CHIP) enrollment reported by the Centers for Medicare & Medicaid Services (CMS) as part of the Performance Indicator Project. It includes data for Medicaid and CHIP and reports enrollment data for children and adults. The data are generally the most recent data available and are useful for reporting trends in Medicaid enrollment. However, the data only capture full-benefit enrollees, excluding those who receive limited benefits, such as those who receive family planning services only, and consequently, do not provide a full count of the total population enrolled in Medicaid. Additionally, these data cannot be used to monitor changes in enrollment by eligibility pathway, including for adults in the Medicaid expansion group.

The 2025 reconciliation law included significant changes to Medicaid, including requiring adults in the expansion group and in certain 1115 waiver programs to meet new work and reporting requirements starting January 2027. These changes are expected to reduce Medicaid enrollment over the next 10 years relative to what would have been expected under current law. Enrollment data for the full Medicaid population is available here, and for more information on how implementation of Medicaid work requirements is affecting Medicaid expansion enrollment, please see Tracking Implementation of the 2025 Reconciliation Law Medicaid Work Requirements.

The figures below show Medicaid and CHIP enrollment from February 2020 through the most current month of available data. Figures include enrollment for adults and children in Medicaid/CHIP and for Medicaid only and CHIP only. Key enrollment data and trends as of May 2026 include:

  • There were 73.5 million people enrolled in Medicaid/CHIP nationally (Figure 1). Medicaid enrollment declined by 5 million or 6% from May 2025 through May 2026 (Table 1).
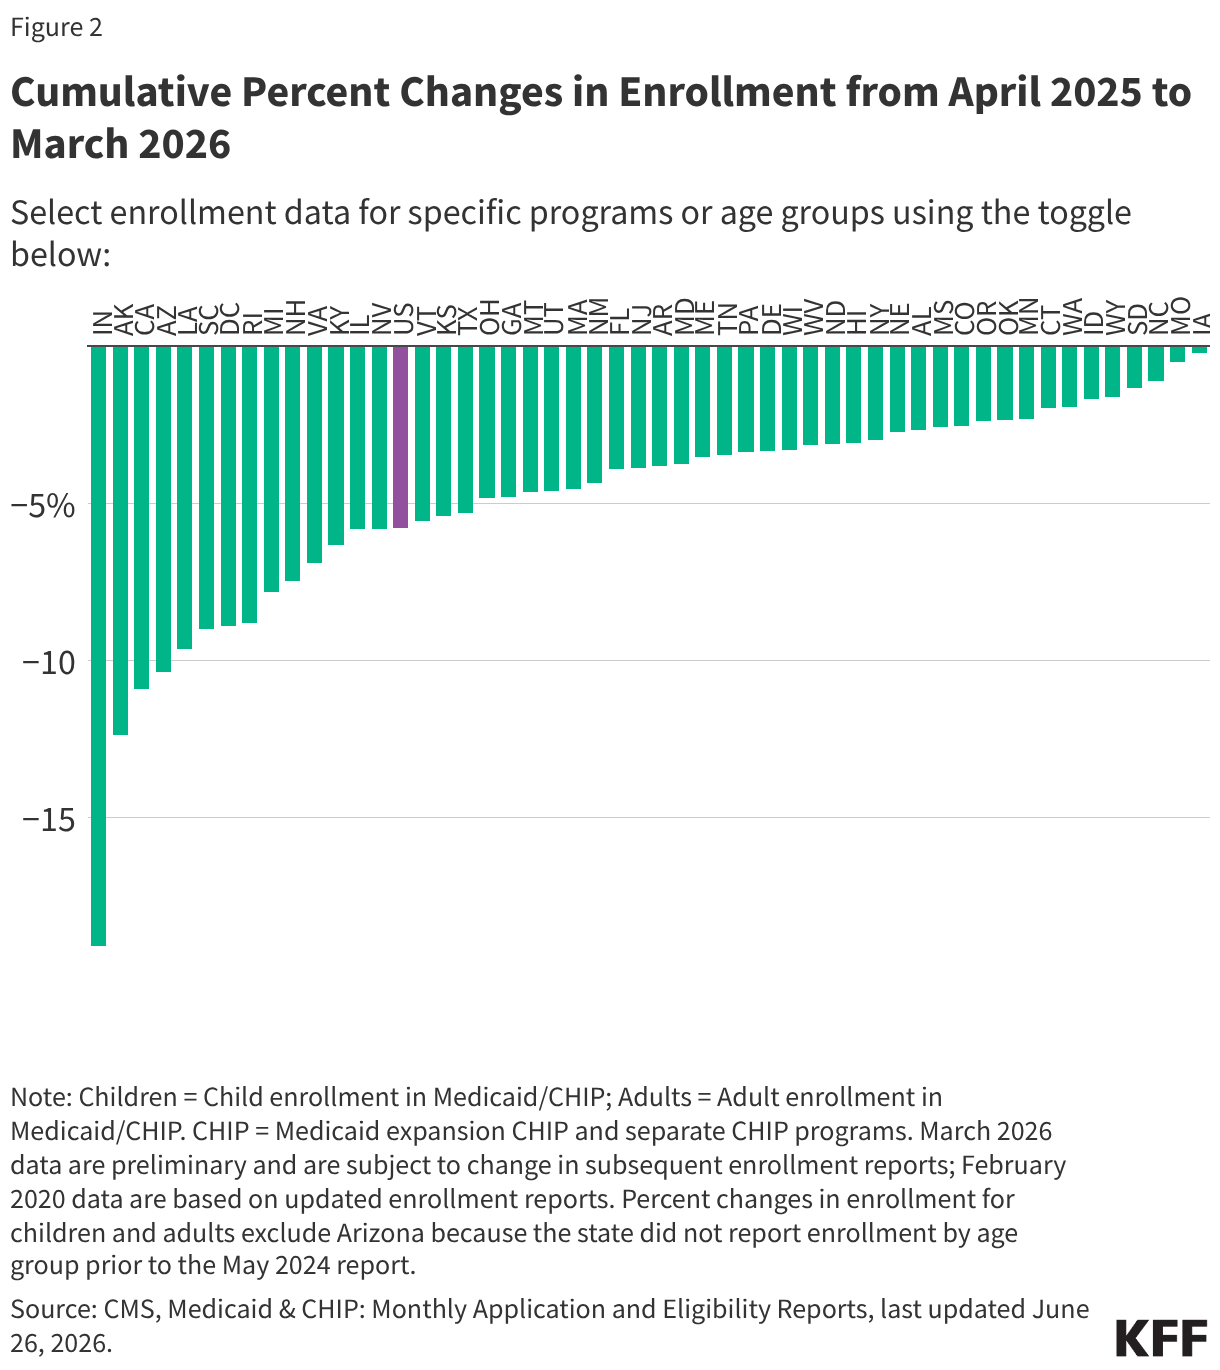
  • Total Medicaid/CHIP enrollment has decreased in 49 states and DC since May 2025. Enrollment changes since May 2025 vary from a less than 1% increase in Iowa to a 20% decrease in Indiana (Figure 2).
  • Child enrollment in Medicaid/CHIP has decreased in 49 states and DC from May 2025 through May 2026. Adult enrollment has decreased in all but five states (IA, MO, NC, OK, SD) (Figure 2).
  • There were 66.4 million people enrolled in Medicaid and 7.1 million people enrolled in CHIP (Figure 1). Since May 2025, Medicaid enrollment has decreased in 49 states and DC while CHIP enrollment has increased in 21 states (AL, CA, CT, DE, FL, HI, IL, MO, NE, NJ, NM, NC, ND, OK, RI, SC, TN, VT, WA, WI, WY).
  • Total Medicaid/CHIP enrollment was 3% higher in May 2026 compared to enrollment in February 2020, prior to the pandemic. However, in the 49 states and DC with complete enrollment data by age, the number of children enrolled in Medicaid/CHIP declined by 789,000 or 2% from February 2020 to May 2026 (Figure 2 and Table 1).
Figure 1
Annual Percent Change in Medicaid/CHIP Enrollment (May 2025 to May 2026) (Column Chart)
Total Medicaid/CHIP Enrollment, Selected Time Periods (Table)

Note: The data on unwinding renewal outcomes presented below were last updated on September 12, 2024; since most states have now completed the Medicaid unwinding, the information will not be updated again.

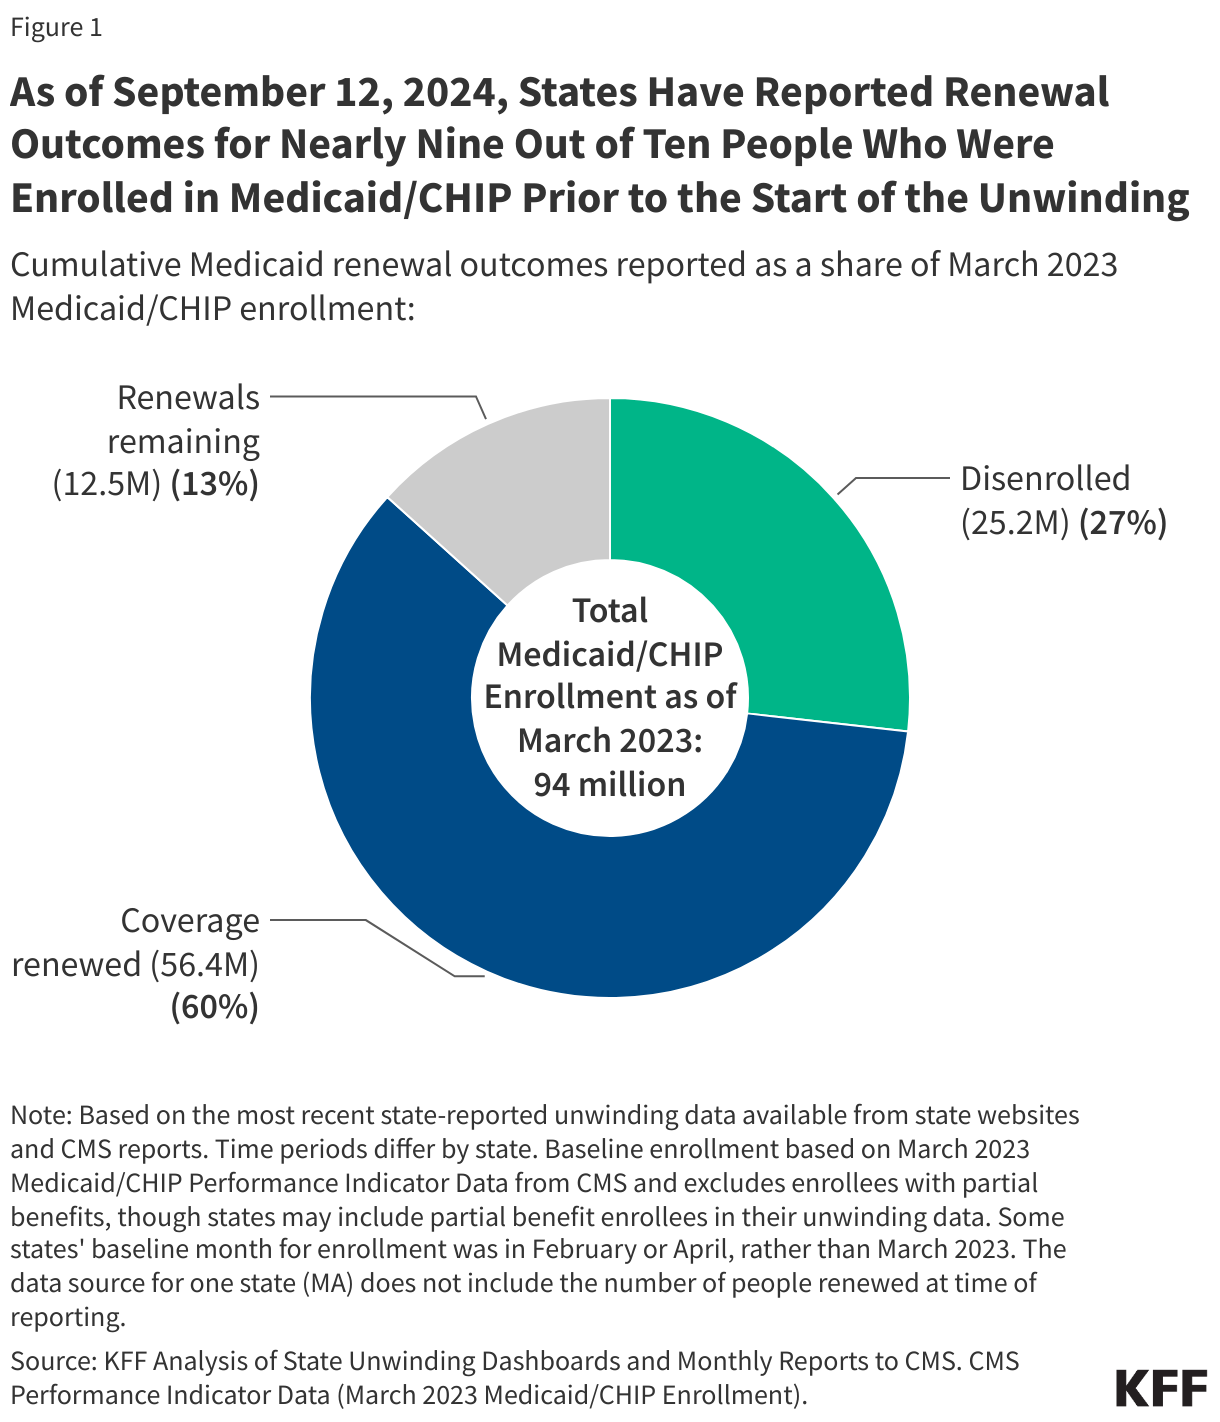
As of September 12, 2024 and with nearly complete unwinding data for most states: 

  • Over 25 million people were disenrolled (31% of completed renewals) and over 56 million people had their coverage renewed (69% of completed renewals).  
  • Disenrollment rates varied across states from 57% in Montana to 12% in North Carolina, driven by a variety of factors including differences in renewal policies and procedures as well as eligibility expansions in some states.  
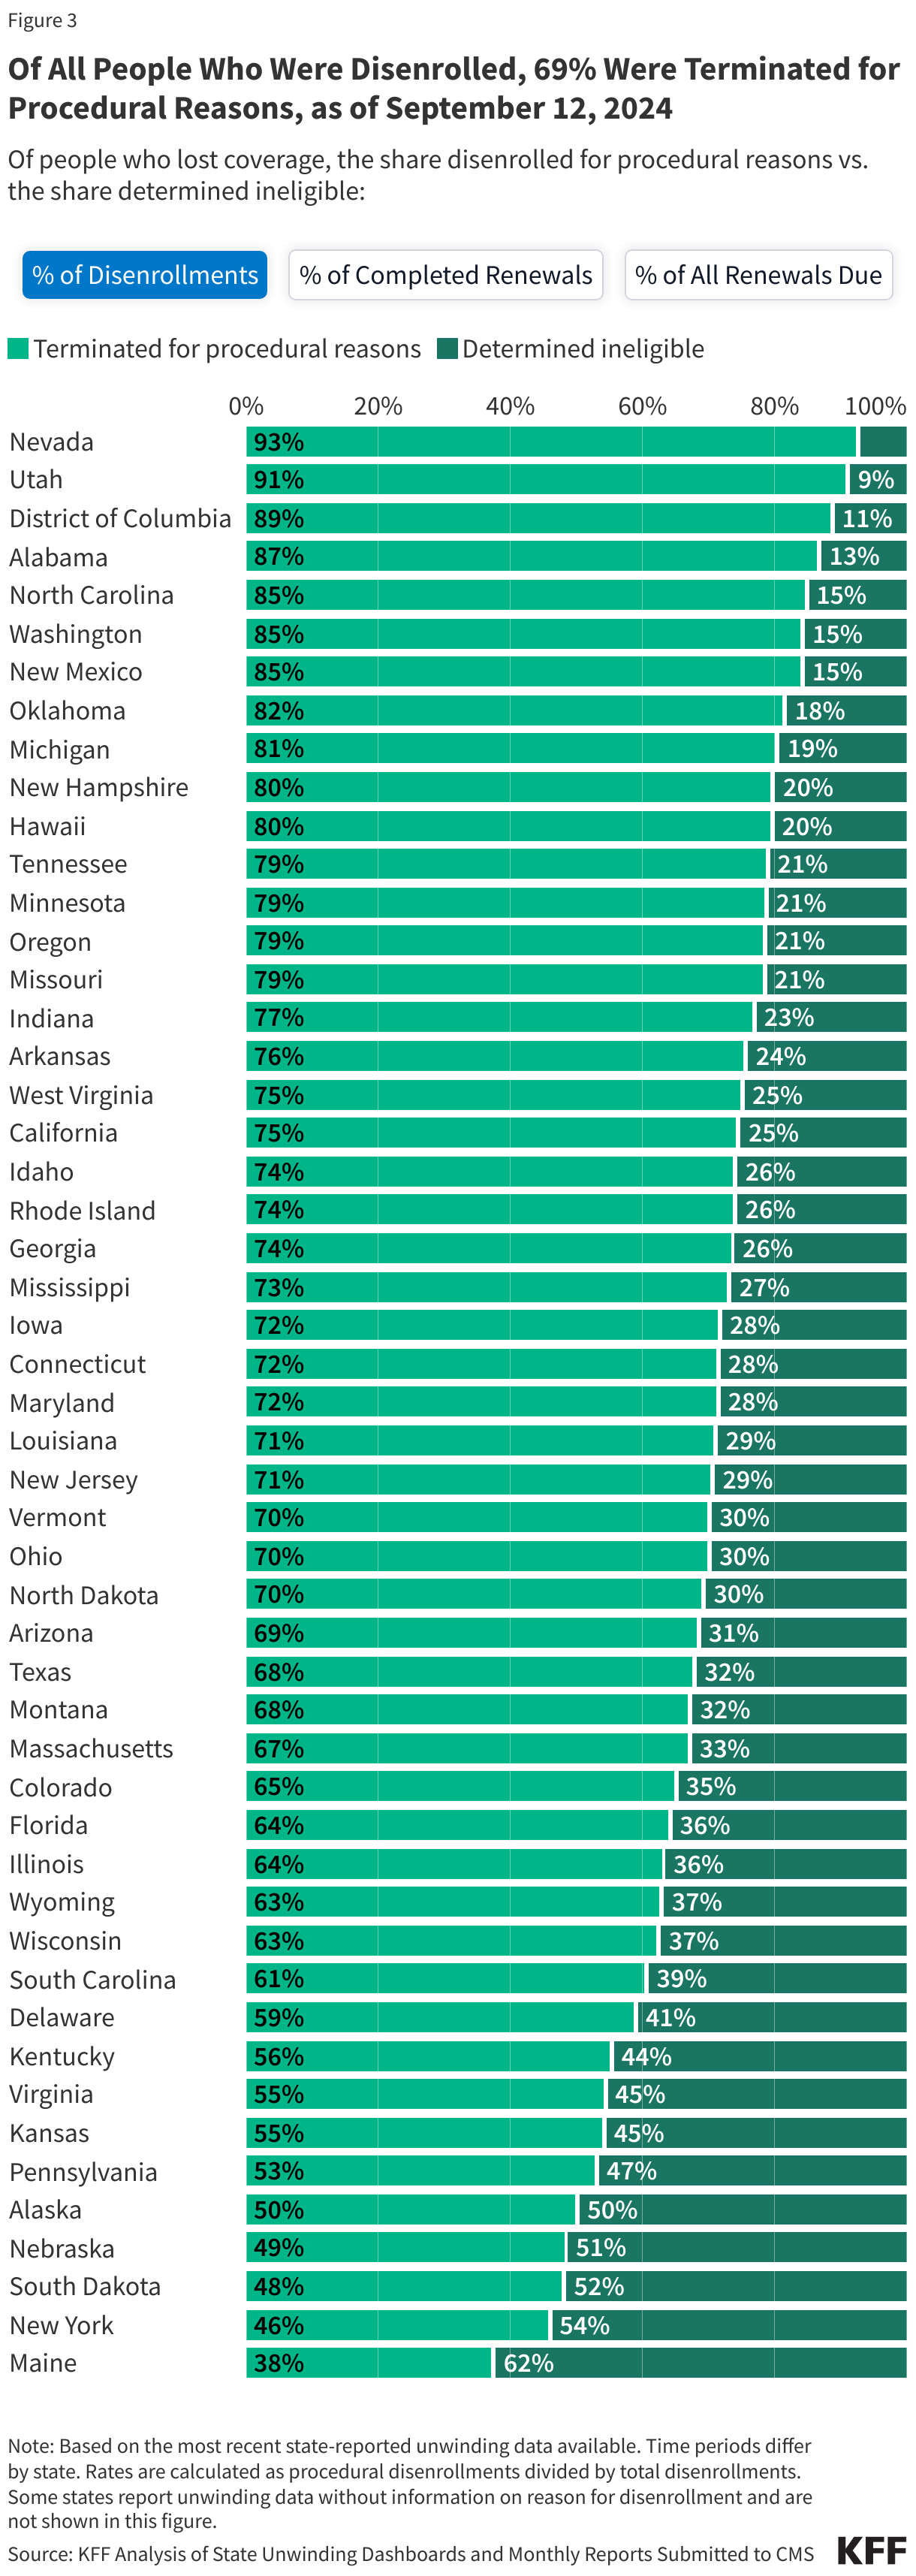
  • Among those who were disenrolled, nearly seven in ten (69%) were disenrolled for paperwork or procedural reasons while three in ten (31%) were determined ineligible.  
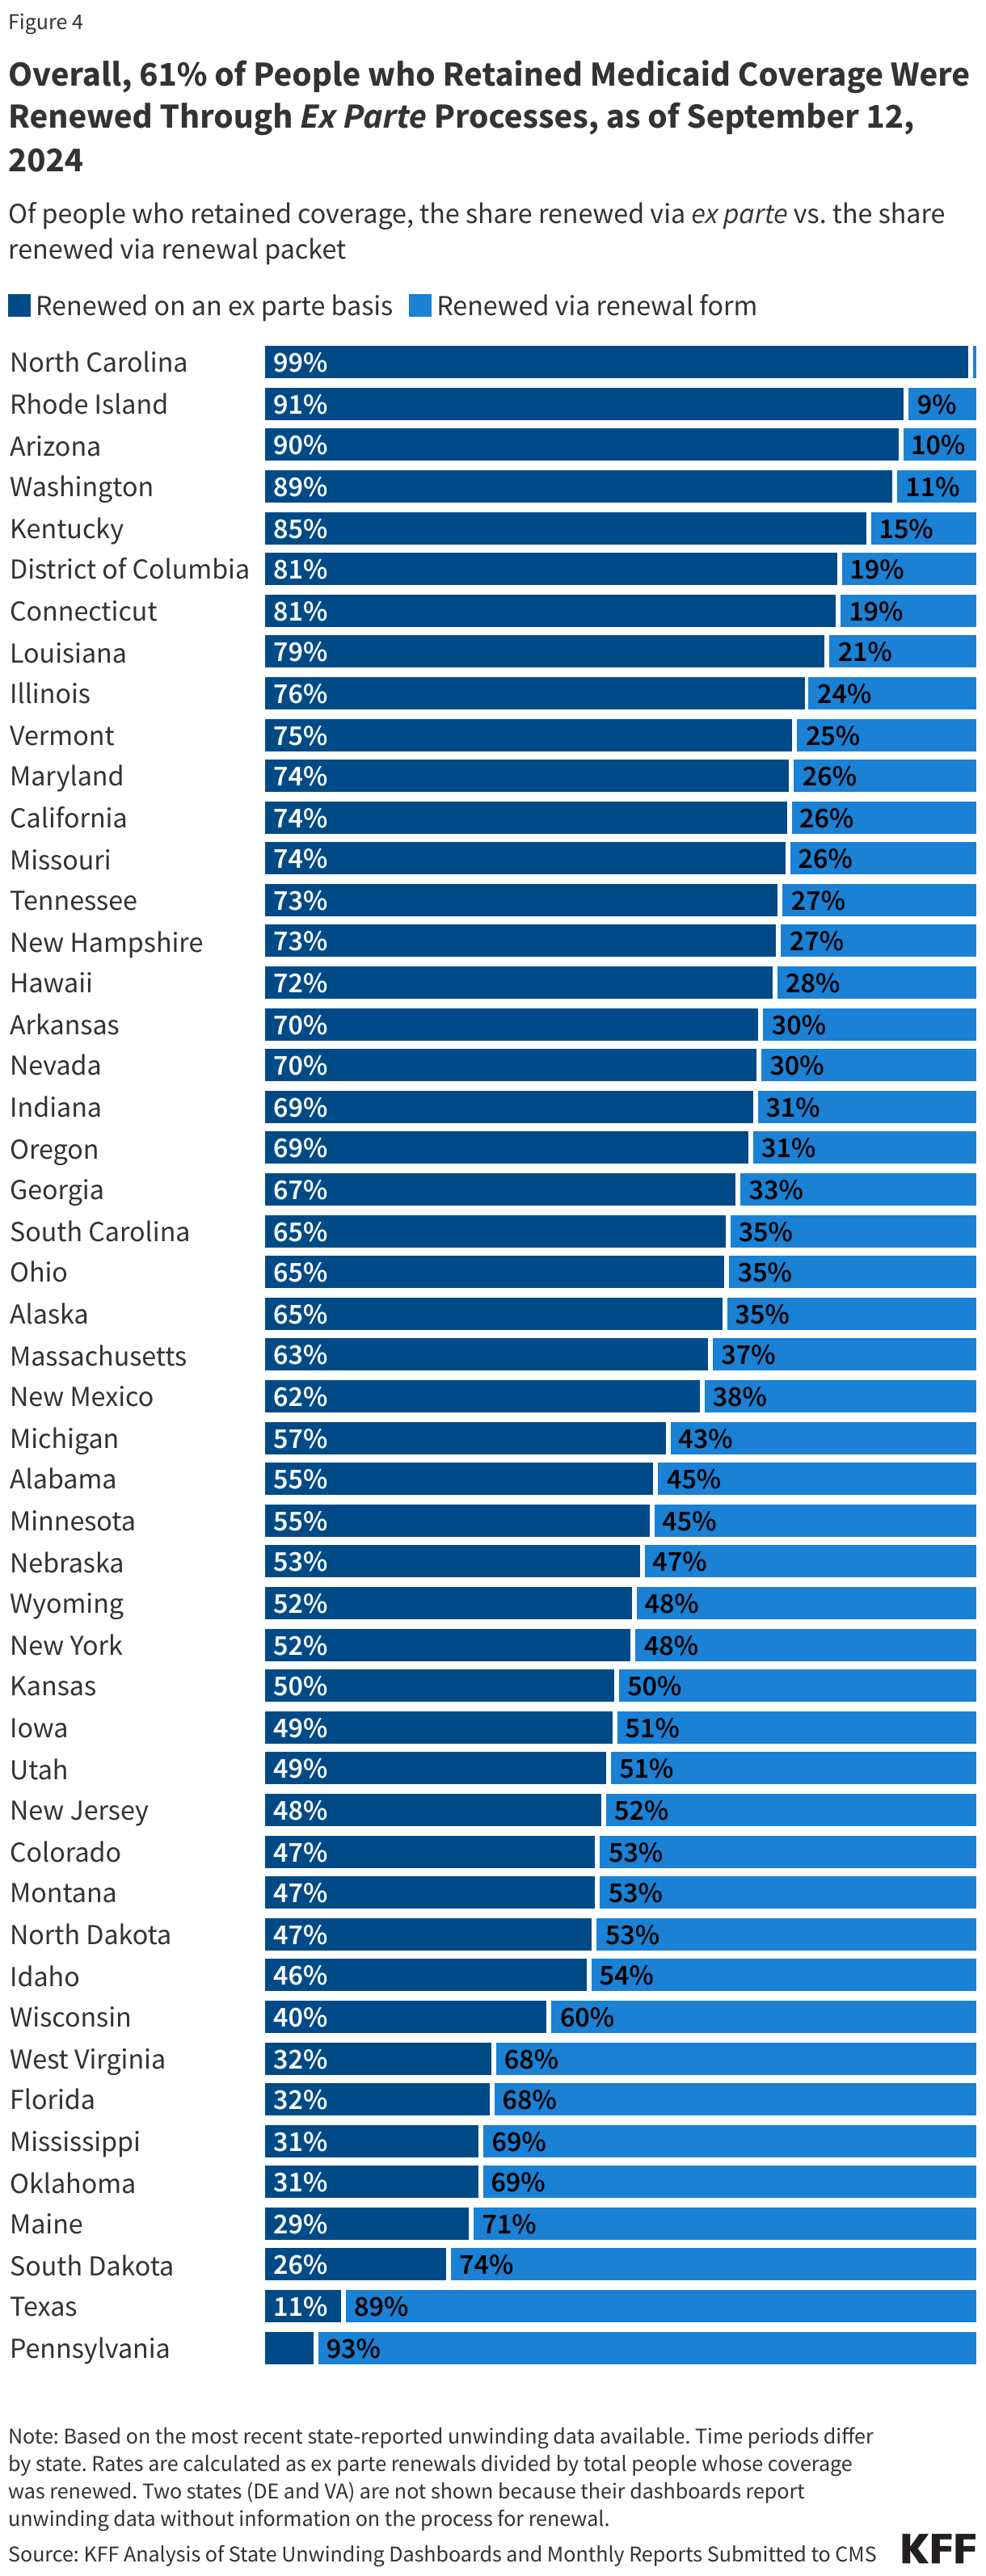
  • Among those whose coverage was renewed during the unwinding, 61% were renewed on an ex parte, or automated, basis, meaning the individual did not have to take any action to maintain coverage. 

State Data on Renewal Outcomes

The data on unwinding-related renewal outcomes presented in this section rely primarily on monthly reports that states were required to submit to the Centers for Medicare & Medicaid Services (CMS) during the unwinding period. The data also reflect updates to the monthly reports that states submit three months after the original report submission to account for the resolution of pending cases and any other changes in renewal metrics. For 13 states, data were pulled from dashboards or reports published on state websites that provide more complete information, and for a few additional states, updated monthly reports were pulled from state websites because they were more timely than what is reported on the CMS website. 

To view archived data for specific states, click on the State Data - Archived tab.


As of September 12, 2024, States Have Reported Renewal Outcomes for Nearly Nine Out of Ten People Who Were Enrolled in Medicaid/CHIP Prior to the Start of the Unwinding (Donut Chart)


Medicaid Disenrollments

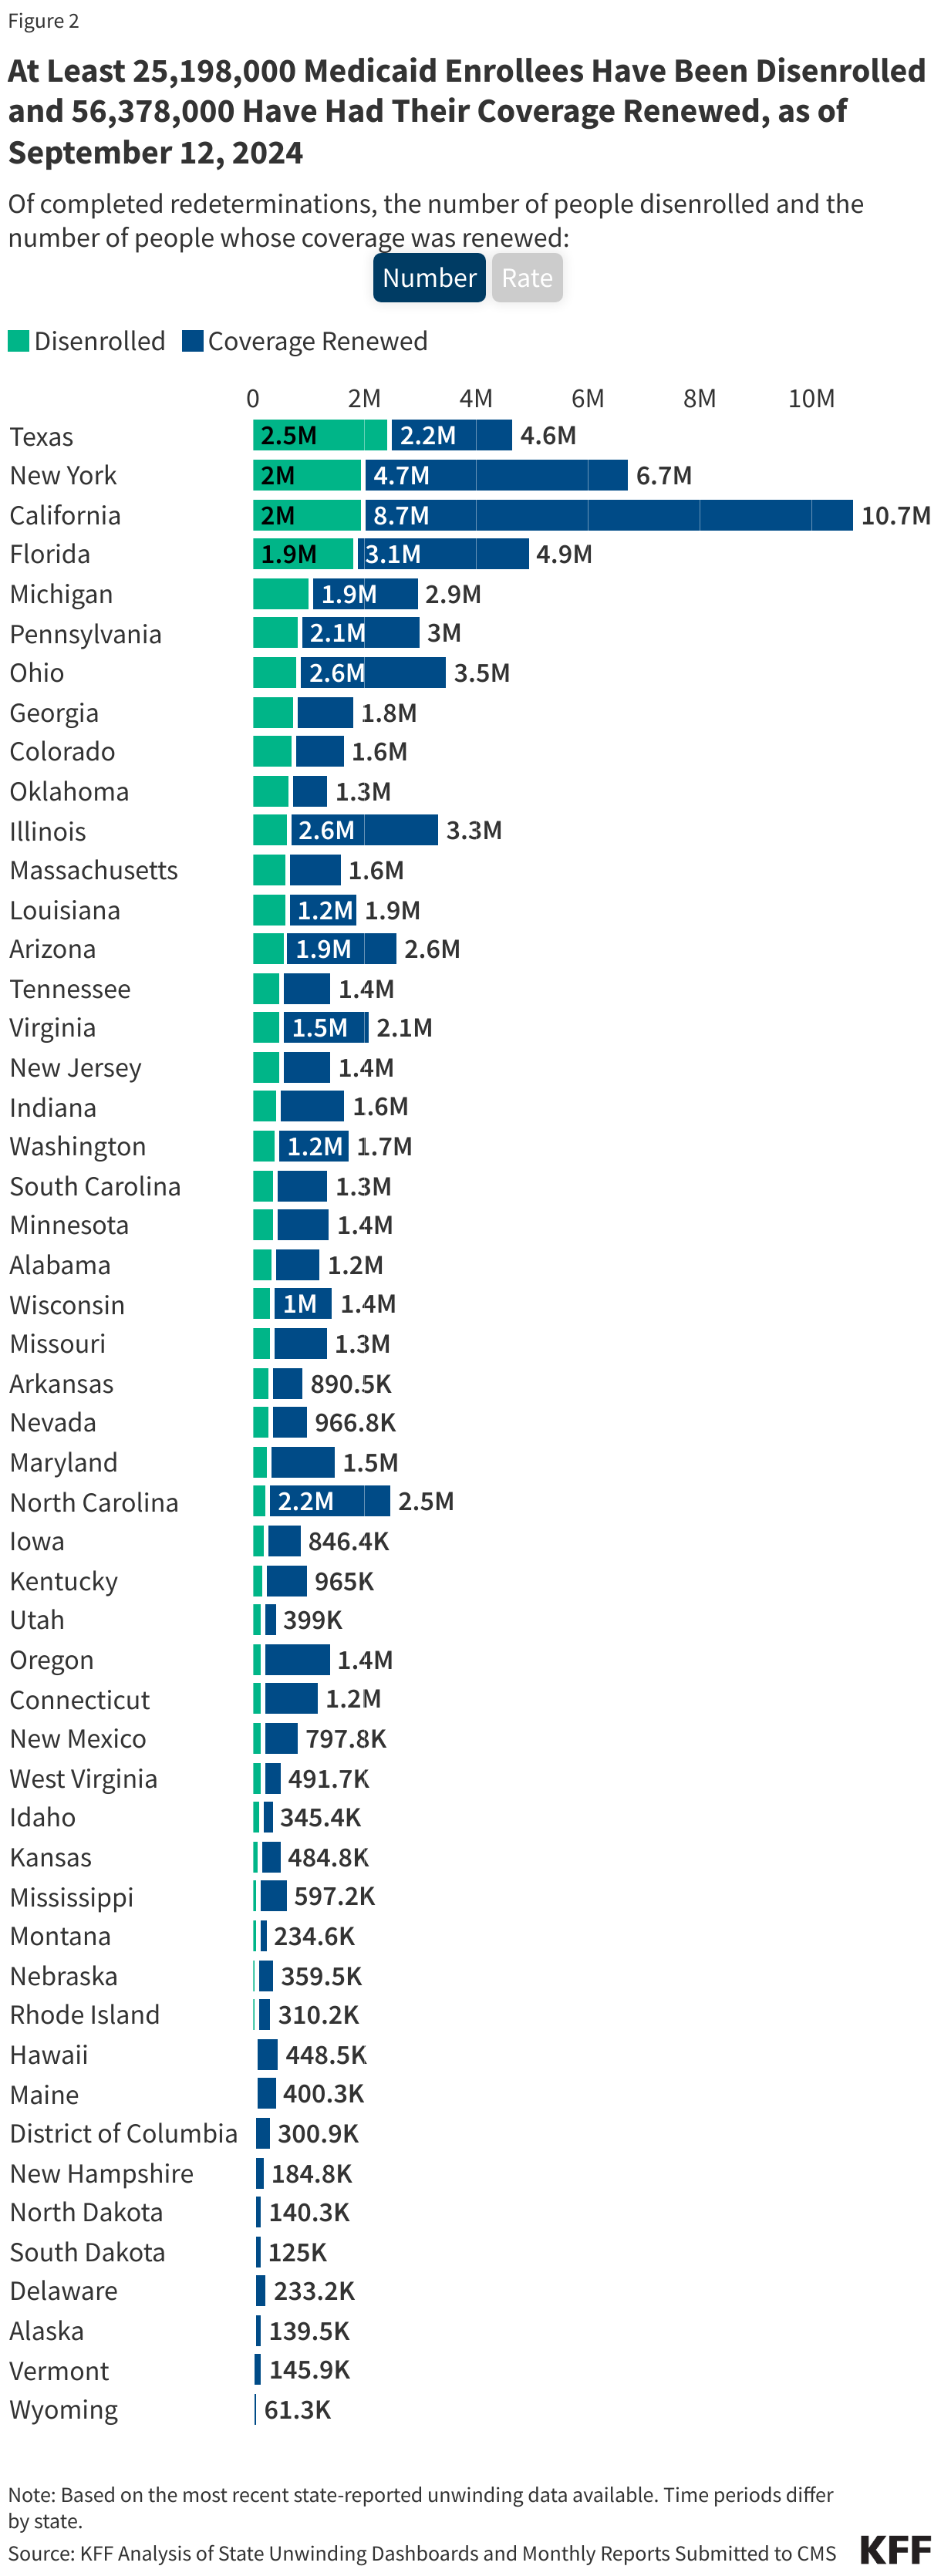
  • As of September 12, 2024, at least 25,198,000 Medicaid enrollees had been disenrolled during the unwinding of the continuous enrollment provision. Overall, 31% of people with a completed renewal were disenrolled in reporting states while 69%, or 56.4 million enrollees, had their coverage renewed.
  • There is wide variation in disenrollment rates across reporting states, ranging from 57% in Montana to 12% in North Carolina. A variety of factors contribute to these differences, including differences in renewal policies and system capacity. Some states adopted policies that promote continued coverage among those who remain eligible and/or have automated eligibility systems that can more easily and accurately process renewals while other states have adopted fewer of these policies and have more manually-driven systems. In addition, North Carolina and South Dakota adopted Medicaid expansion and other states increased eligibility levels for certain populations (e.g., children, parents, etc.) during the unwinding, which may have lowered disenrollment rates in these states.

At Least 25,198,000 Medicaid Enrollees Have Been Disenrolled and 56,378,000 Have Had Their Coverage Renewed, as of September 12, 2024 (Stacked Bars)


  • Across all states with available data, 69% of all people disenrolled had their coverage terminated for procedural reasons. However, these rates vary based on how they are calculated (see note below). Procedural disenrollments are cases where people are disenrolled because they did not complete the renewal process and can occur when the state has outdated contact information or because the enrollee does not understand or otherwise does not complete renewal packets within a specific timeframe. High procedural disenrollment rates are concerning because many people who are disenrolled for these paperwork reasons may still be eligible for Medicaid coverage. 

(Note: The first tab in the figure below calculates procedural disenrollment rates using total disenrollments as the denominator. The second tab shows these rates using total completed renewals, which include people whose coverage was terminated as well as those whose coverage was renewed, as the denominator. And finally, the third tab calculates the rates as a share of all renewals due, which include completed renewals and pending cases.)

Of All People Who Were Disenrolled, 69% Were Terminated for Procedural Reasons, as of September 12, 2024 (Stacked Bars)

Medicaid Renewals

  • Of the people whose coverage has been renewed as of September 12, 2024, 61% were renewed on an ex parte basis while 39% were renewed through a renewal form, though rates vary across states. Under federal rules, states are required to first try to complete administrative (or “ex parte”) renewals by verifying ongoing eligibility through available data sources, such as state wage databases, before sending a renewal form or requesting documentation from an enrollee. Ex parte renewal rates varied across states from 90% or more in Arizona, North Carolina, and Rhode Island to less than 20% in Pennsylvania and Texas. 

Overall, 61% of People who Retained Medicaid Coverage Were Renewed Through Ex Parte Processes, as of September 12, 2024 (Stacked Bars)

Federal Data on Renewal Outcomes

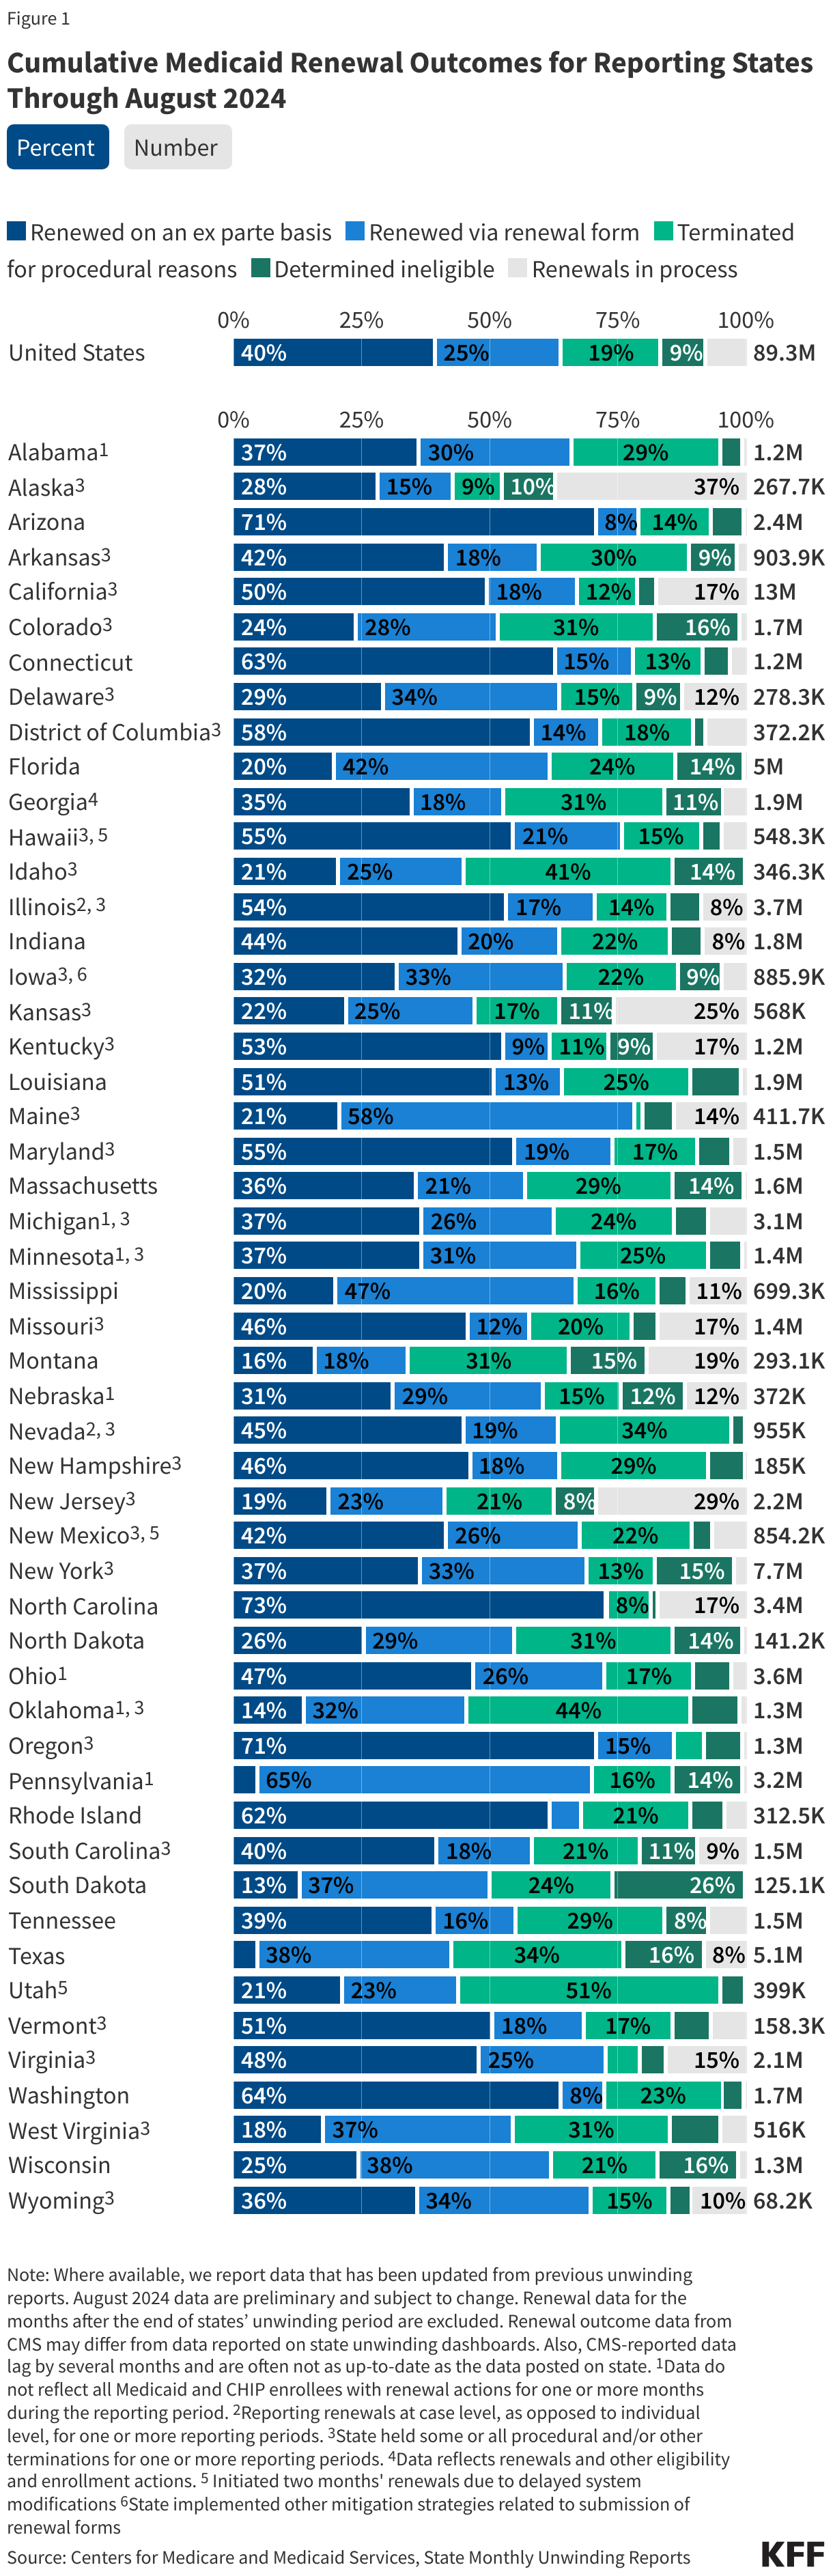
The data presented here are cumulative unwinding metrics published by CMS. These counts and percentages may differ from the above data, which present renewal metrics reported on state websites when state-reported data are more complete.  

Figure 1 below shows cumulative renewal data reported by CMS during states’ unwinding periods. Renewal data for the months after the end of states’ unwinding period are excluded. The data reflect updated unwinding data reported by states three months after the original monthly reports as they become available.   

Cumulative Medicaid Renewal Outcomes for Reporting States Through August 2024 (Stacked Bars)

For questions about this tracker, please contact KFFTracker@kff.org

State Unwinding Data - Archived

Note: The state data presented below were last updated on September 12, 2024; since most states have now completed the Medicaid unwinding, the information will not be updated again. 

The data presented here provide state-level data on enrollment trends and renewal outcomes during the unwinding period. Figure 1 shows total Medicaid enrollment by month starting in January 2023 and, once disenrollments resumed in a state, the cumulative percent change in Medicaid enrollment relative to the month before Medicaid disenrollments started (this baseline month will differ across states). Figure 2 shows renewal metrics for each month of a state’s unwinding period (or cumulative data for the unwinding period for some states). 

For total national Medicaid enrollment, click on the Enrollment Data tab.

Related Resources - Archived

Resources on unwinding data

Resources on state policies and preparations for the unwinding

Resources on pre-pandemic enrollment patterns and coverage transitions

KFF’s unwinding explainer

The Business of Health with Chip Kahn

AI’s Role in Health Care: What Keeps You Up at Night?

September 8, 2026

Video

Audio

About this Episode


Episode 14, AI Series: At the close of every episode, Chip asks his guests the same question: ‘What keeps you up at night?’ In this highlights episode, we share intriguing responses on AI’s role in health care. From deepfakes and misinformation to bias and the risk of losing the human connection at the heart of care, these highlights capture some of the top issues today.

The Host


Headshot photo of Chip Kahn wearing a navy blue suit with a red tie, red pendant on lapel, and glasses.

Sr. Visiting Fellow

Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.


SERIES

This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.

The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.

KFF Survey Methodology & Data Collection Standards

Published: Aug 28, 2026

About Our Surveys

 KFF has a long history of conducting public opinion polls to amplify the public’s voice in policy debates, including groups that are under-researched and under-reported. For the past three decades, KFF’s polling work has combined both rigorous methodology and transparency. Every survey we publish is accompanied by a full methodology statement and topline results, so readers can see details about how the data was collected, read every question included in the survey in the order in which they were asked, and judge its quality for themselves.  

 While asking the public about political issues and candidates is an important part of our polling work, KFF does not conduct “horse race” polling with the goal of predicting election outcomes. Our election-related polling focuses on how the public thinks about health care issues when making voting decisions, not on forecasting who might win.  While certain things about our survey methods change from project to project, the principles of our methodology are consistent and described below. To find more details for each survey, check out the “Topline & Methodology” link at the top right of each survey project on our website. 

How We Reach People 

 KFF surveys rely almost exclusively on probability-based sampling, meaning respondents are selected at random rather than choosing to participate on their own. Most of our national population surveys use a sampling approach that combines two sample types: 1) a probability-based panel and 2) a random digit dial sample of pre-paid cell phone numbers.  

 Probability-based panel members are recruited through random sampling, using two main methods: mailed invitations sent to addresses randomly selected from U.S. Postal Service delivery records, and random digit dialing of cell phone numbers. This means that, in principle, every U.S. adult has a known chance of being invited to join the panel, whether or not they were looking to take a survey. Once someone joins the panel, they can complete our surveys online, by phone, or in some cases by text message invitation to a web survey. This hybrid approach helps us reach people who might otherwise be left out of an online-only survey, including older adults, people with lower incomes, and people without reliable internet access. KFF works with multiple probability-based panels including the SSRS Opinion Panel, Ipsos Knowledge Panels, and NORC AmeriSpeak.  

For most projects, we supplement probability-based panels with a sample of random digit dialed pre-paid cell phone numbers. Pre-paid or “pay as you go” cell phone numbers are used disproportionately by population groups that respond at lower rates to traditional survey methods, including young Black and Hispanic men, and people who do not speak English. Combining these sample types helps our surveys be more representative of the diversity of the national population, not just those who are easiest to reach.  

Our national survey projects are conducted in English and Spanish, usually fielded over 5-6 days so people have more time to respond, and provide small financial incentives for individuals who participate, to help bring in those who might otherwise skip a survey. Without these steps, surveys run the risk of overrepresenting the most engaged or opinionated members of the public.   

In addition, KFF conducts deeper surveys on populations that general population polling cannot adequately capture. These projects start from the same principle as our general population surveys: probability-based sampling, whether through probability-based panels, address-based recruitment, voter registration lists, or purpose-built panels of previous respondents, adapted to fit the population being studied. Reaching a small, specific, or hard-to-reach group often requires fielding a survey in more languages, using more modes of contact, and longer field periods. 

How We Work To Be Representative 

Even with a well-designed sampling frame, most polls will not perfectly mirror the population on every characteristic, so we use statistical techniques to adjust, or weight, the results to align with known population benchmarks from sources like the Census Bureau on measures such as age, gender, race and ethnicity, education, and region. Weighting corrects for the fact that some groups are easier to reach than others and helps ensure that no single group is overrepresented or underrepresented in the final results.  

All KFF survey reports include margins of sampling error for the total sample and key subgroups, which reflect the statistical uncertainty that comes with asking questions of a sample rather than every single member of the population. In addition to sampling error, all public opinion polls may be subject to other types of error such as question wording effects, nonresponse bias, or mode effects.  

Our Polling Expertise and News Partnerships 

KFF has a team of polling experts who design our surveys, write questionnaires, analyze data, and write reports. This team works closely with KFF health policy experts who contribute their knowledge on issues like health reform, ACA, Medicare, Medicaid, women’s health, global health, and other issues to the survey design and reporting process.  

We don’t commission others to conduct polling on our behalf or undertake surveys on behalf of other organizations. We contract with outside organizations to perform survey fieldwork and statistical weighting, which is paid for through KFF’s endowment and sometimes using funds from outside funders. KFF maintains full editorial control over all its policy analysis, polling, and journalism activities, regardless of funding source. 

Some of our surveys are conducted in partnership with major news organizations in order to help KFF magnify its polling by combining survey data with in-depth journalism and storytelling, an approach that KFF has used since 1995. KFF and its partners choose survey topics together and design the survey instrument with input from both organizations while retaining full editorial independence over what each organization publishes. 

Artificial Intelligence in Survey Research 

KFF uses Artificial Intelligence (AI) in specific ways to strengthen our work and we publicly disclose when we’ve used AI in a way that is central to our survey methods. For example, we often use AI tools (with human oversight) to assist with coding of open-ended survey responses into discrete categories. KFF does not use AI to create or model “synthetic” public opinion. Every survey we field is grounded in real interviews with human respondents, selected through probability-based sampling, never generated, simulated, or estimated by AI standing in for actual human answers. 

Our Commitment to Methodological Transparency

KFF public opinion and survey research is a charter member of AAPOR’s Transparency Initiative. The American Association for Public Opinion Research (AAPOR) Code of Professional Ethics and Practices commits members to maintain the highest standards of scientific competence, integrity, accountability, and transparency in designing, conducting, analyzing, and reporting their work, and requires researchers to disclose sufficient information about how the research was conducted to allow for independent review and verification of research claims, regardless of the methodology used. 

Excellent survey research is not just about getting people to answer questions, it is about making sure the estimates are representative, can hold up to scrutiny, and are collected in a way that respects the people who take the time to answer. As trust in institutions, including in survey research itself, continues to decline, KFF remains committed to the methods that have proven most reliable over decades of public opinion research: random selection, careful weighting, and full transparency about how the work gets done. Reach out if you have any questions about our polls or our methodology.