Tennessee Plans to Share Data on Children with Disabilities with Immigration Authorities

Published: Jun 29, 2026

According to recent news reports, the families of about 400 children with disabilities who are enrolled in Tennessee’s Children’s Special Services (CSS) program received notices from the state health department in early June stating that if their child continued to remain enrolled in CSS beyond June 30, 2026, their information would be reported to a central state immigration enforcement agency. However, following a lawsuit filed by physicians in the state, a judge issued a temporary restraining order on June 24, 2026, to prevent this data sharing from taking place. Tennessee is one of at least six states that have taken actions as of June 2026 to require state agencies to report applicants or recipients of Medicaid and/or other public benefits whose immigration status could not be verified and/or who were verified to not have lawful presence with immigration enforcement authorities. Under longstanding federal law, Medicaid and other federally funded health coverage are already limited to lawfully present immigrants.

In Tennessee, the legislation requires every state governmental entity, local governmental entity, and local health department to verify that each applicant who is 18 years of age or older and applies for a federal, state, or local public benefit is a United States citizen or lawfully present immigrant. It also requires these entities to report all identifying information for individuals who are not lawfully present and who receive federal, state, or local public benefits to the state’s centralized immigration enforcement division and makes it a criminal offense for an employee or official to intentionally fail to report an individual who is not lawfully present.

Tennessee has interpreted this law to include its CSS program, although Tennessee Representative Steve Cohen wrote a letter to Governor Bill Lee indicating that the law reads as limited to applicants who are at least 18 years old. Tennessee’s CSS program provides care coordination and payment assistance for certain services to people under age 21 whose family income is at or below 225% of the federal poverty level and who have a physical disability, such as cerebral palsy, cystic fibroses, sickle cell anemia or other serious medical conditions without immigrant eligibility restrictions. A recent report indicates more than 4,600 children in Tennessee are enrolled in CSS.

Health care providers and advocates in the state have warned that this data sharing will likely lead families to stop participating in the program, which could lead to disruptions in care that have life threatening consequences. Reporting requirements could also have “chilling effects” that lead to disenrollment and forgone enrollment among a broader group of families than those subject to the new reporting requirements due to confusion and fear. 

A 2025 national KFF survey shows that the share of immigrant adults who said they avoided applying for a government program that helps pay for food, housing, or health care in the past 12 months because they did not want to draw attention to their or a family member’s immigration status rose from 8% to 12% between 2023 and 2025. Further, 11% of immigrant adults say they have stopped participating in such a program since January 2025 because of immigration-related worries, including about four in ten (42%) of those who are likely undocumented and about one in six (17%) parents. Moreover, about half (51%) of immigrant adults overall and about eight in ten (78%) of those who are likely undocumented said they are “somewhat” or “very” concerned about health officials or providers sharing patient information with immigration enforcement officials (Figure 1). These data were collected prior to recent state-level actions to share data on immigrant families with immigration enforcement officials.
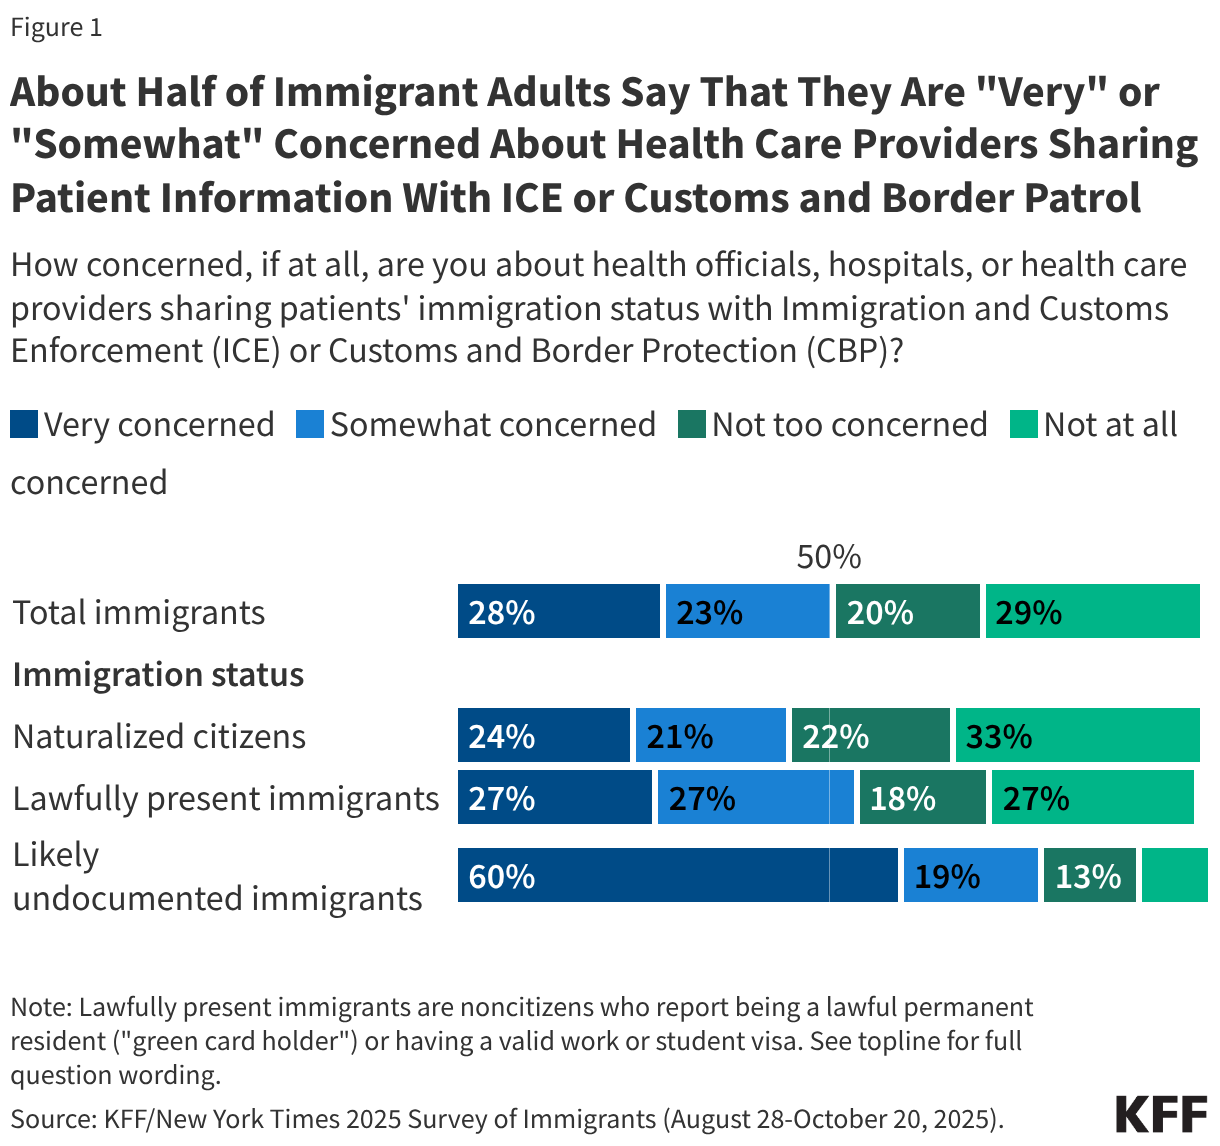
About Half of Immigrant Adults Say That They Are "Very" or "Somewhat" Concerned About Health Care Providers Sharing Patient Information With ICE or Customs and Border Patrol (Stacked Bars)

Beyond the data sharing actions in Tennessee and several other states, in July 2025, the Centers for Medicare and Medicaid Services (CMS) and U.S. Immigration and Customs Enforcement (ICE) established an Information Exchange Agreement that enables immigration enforcement officials to access the personal data of millions of Medicaid enrollees to help identify and locate “aliens in the United States.” This data sharing represents a reversal in prior policy that asserted CMS would not share such information and ICE would not use such information for immigration enforcement purposes, with assurances made to the public, applicants and enrollees, health care providers, and states that information collected to determine eligibility for health coverage programs would not be used for immigration enforcement. The administration also has directed the Internal Revenue Service to share personal information of individuals for immigration enforcement purposes, although these actions are facing court challenges.
Nearly Four Million Medicare Beneficiaries Met the Eligibility Criteria in 2023 for the Medicare GLP-1 Bridge

Published: Jun 29, 2026

On July 1, 2026, the Centers for Medicare & Medicaid Services (CMS) will roll out a new, temporary program covering GLP-1s for obesity for people with Medicare. The program, known as the Medicare GLP-1 Bridge, provides coverage of GLP-1s used for weight reduction and weight management to eligible beneficiaries enrolled in Medicare Part D, although the program will operate outside of the Part D benefit and payment system. Under the Medicare GLP-1 Bridge, eligible beneficiaries can get Medicare coverage of GLP-1s for obesity for a $50 monthly copayment, which will not count towards the Part D deductible or out-of-pocket spending cap and Part D Low-Income Subsidy cost-sharing assistance will not apply. The temporary program, running from July 2026 through December 2027, does not change the current statutory prohibition on Medicare coverage of drugs used for weight loss but instead is being established using the federal government’s Section 402 demonstration authority.

The Medicare GLP-1 Bridge will provide coverage of three GLP-1s (Wegovy, Zepbound, and Foundayo) that have been approved by the FDA for chronic weight management in adults with obesity (BMI of 30 or more) or adults with overweight (BMI of 27 or more) plus a weight-related comorbid condition. The clinical criteria for determining eligibility for the Medicare GLP-1 Bridge are somewhat more restrictive than the FDA approvals, however, and include Part D enrollees with a BMI of 35 or more; with a BMI of 30 or more and heart failure with preserved ejection fraction, uncontrolled hypertension, or chronic kidney disease stage 3a or above; or with a BMI of 27 or more and pre-diabetes, previous myocardial infarction, previous stroke, or symptomatic peripheral artery disease.

Eligibility for the Medicare GLP-1 Bridge will also be limited to Medicare beneficiaries who have not filled a prescription under their Part D plan for a GLP-1 in 2026, and who do not have a diagnosis with a condition that is a medically accepted indication for a GLP-1 drug that could be covered under Part D (specified by CMS as type 2 diabetes, obstructive sleep apnea (OSA), and noncirrhotic metabolic dysfunction-associated steatohepatitis (MASH)), even if they otherwise meet the clinical criteria. These limits are designed to prevent GLP-1 use that could be covered under Part D from shifting to the Medicare GLP-1 Bridge and will also help to limit the cost of the program to Medicare. As part of the prior authorization process for Bridge, prescribing clinicians will need to attest that the GLP-1 prescription is for weight reduction and weight management and that beneficiaries meet the clinical criteria and do not have a diagnosis of type 2 diabetes, OSA, or MASH that would make them eligible for GLP-1 coverage under Part D.

CMS has not released an estimate of how many beneficiaries could be eligible for the Medicare GLP-1 Bridge, although the director of Medicare at CMS, Chris Klomp, recently stated the agency anticipates the program will start with “single-digit millions” of beneficiaries. This analysis uses 2023 Medicare claims for traditional Medicare, Medicare Advantage encounter data, and Part D prescription drug event data to estimate the total number of Medicare beneficiaries with obesity or overweight, the number of Part D enrollees who met the Bridge eligibility criteria in 2023, and those who met the Bridge clinical criteria but who also had diagnoses recorded in claims or encounter data that would qualify for Part D coverage of GLP-1s (type 2 diabetes, OSA, or MASH) or who had a GLP-1 Part D-covered prescription during the year, either of which would make them ineligible for Bridge (see Methods).

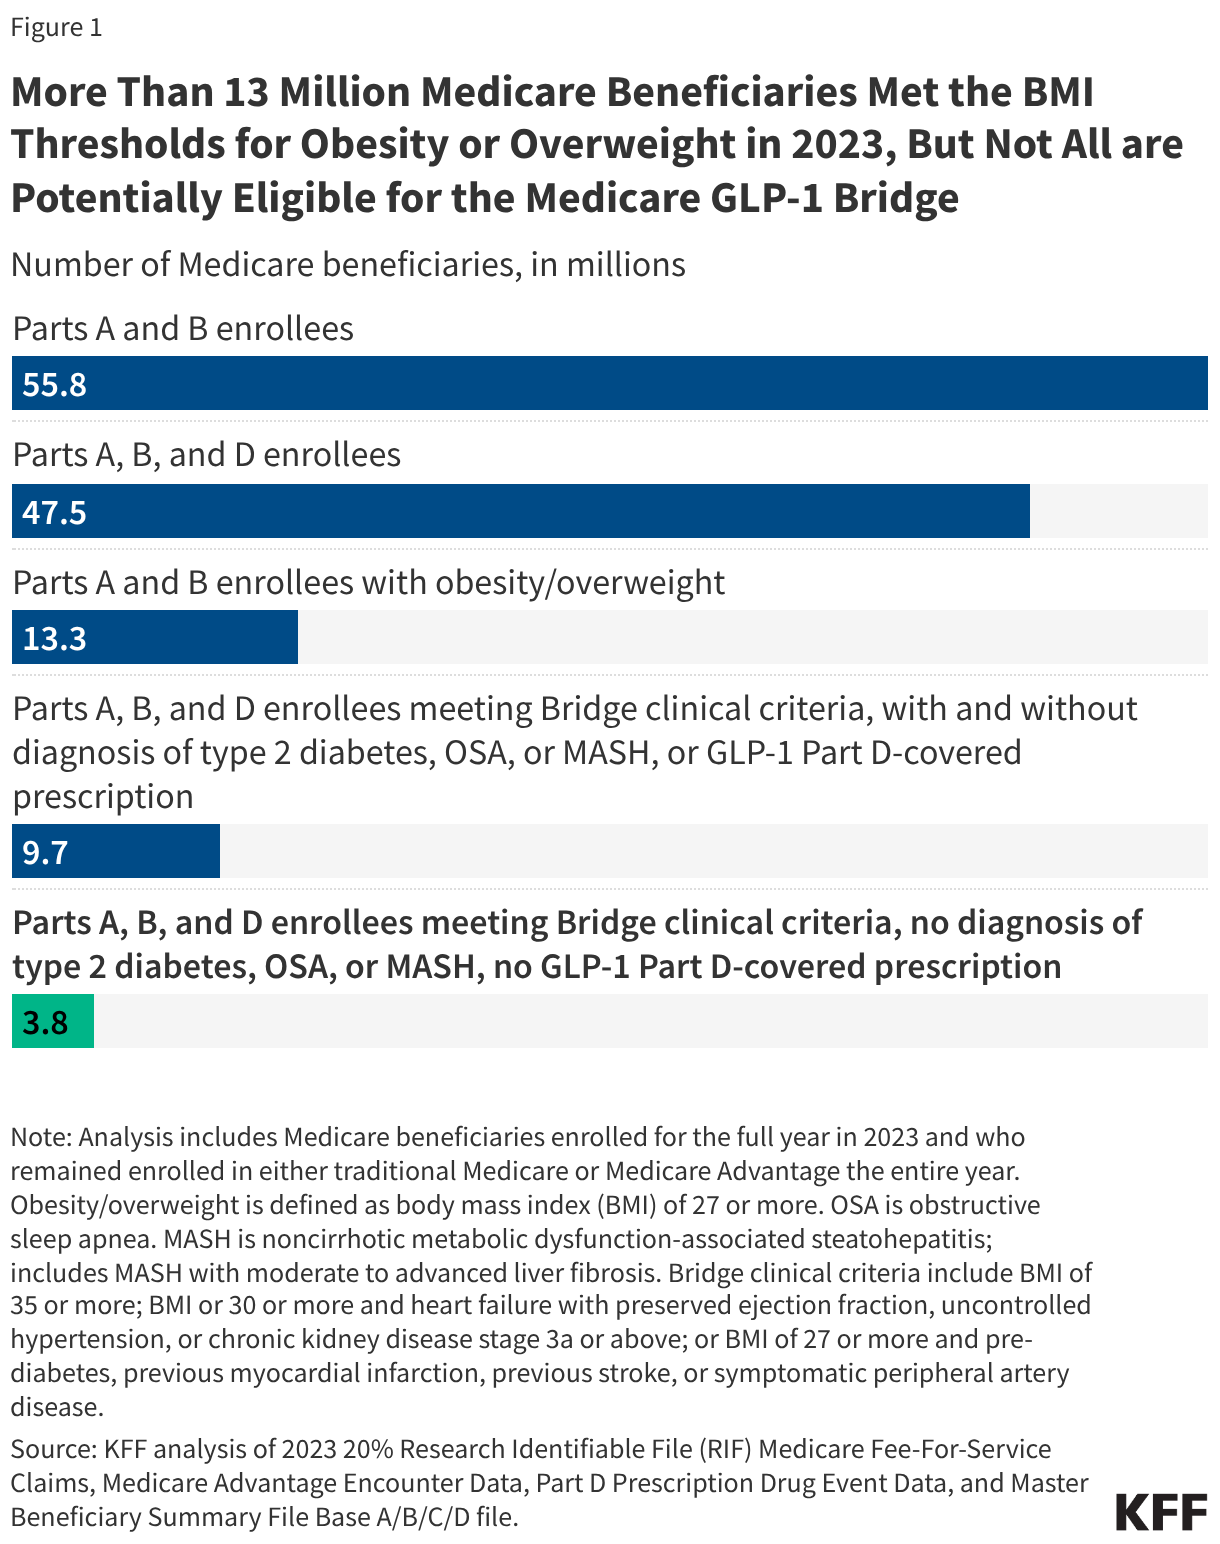
More than 13 million Medicare beneficiaries met the BMI thresholds for obesity or overweight in 2023, but not all are potentially eligible for the Medicare GLP-1 Bridge. In 2023, an estimated 13.3 million Medicare beneficiaries enrolled in Parts A and B had obesity or overweight, based on having BMI of 27 or more recorded in claims or encounter data, or 24% of Medicare beneficiaries overall (Figure 1). (This estimate could be conservative to the extent that not all beneficiaries with obesity or overweight may have a claims-based diagnosis.) However, the potentially eligible population for the Medicare GLP-1 Bridge is not as broad as if the program were targeted to all people with Medicare with obesity or overweight. As detailed below, an estimated 3.8 million beneficiaries could be eligible for Bridge as of 2023, based on meeting all the eligibility criteria.

More Than 13 Million Medicare Beneficiaries Met the BMI Thresholds for Obesity or Overweight in 2023, But Not All are Potentially Eligible for the Medicare GLP-1 Bridge (Bar Chart)

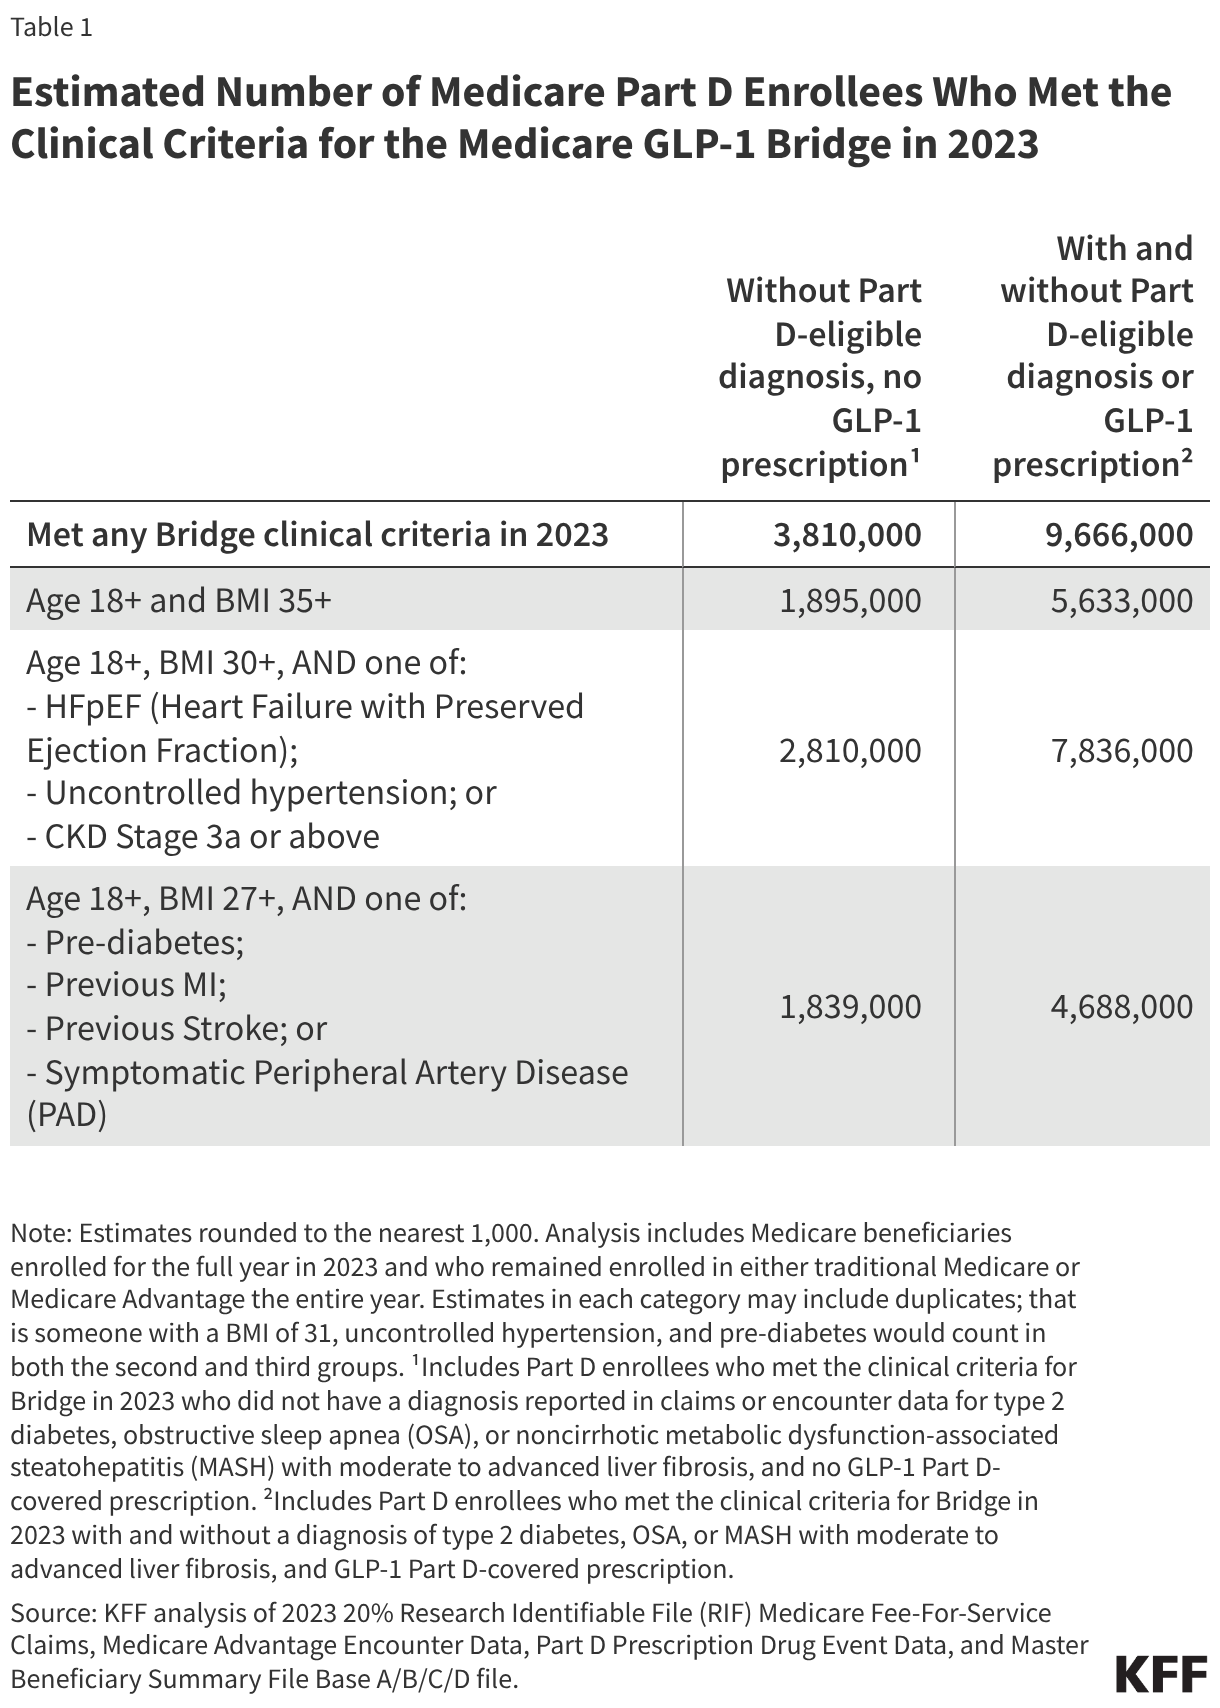
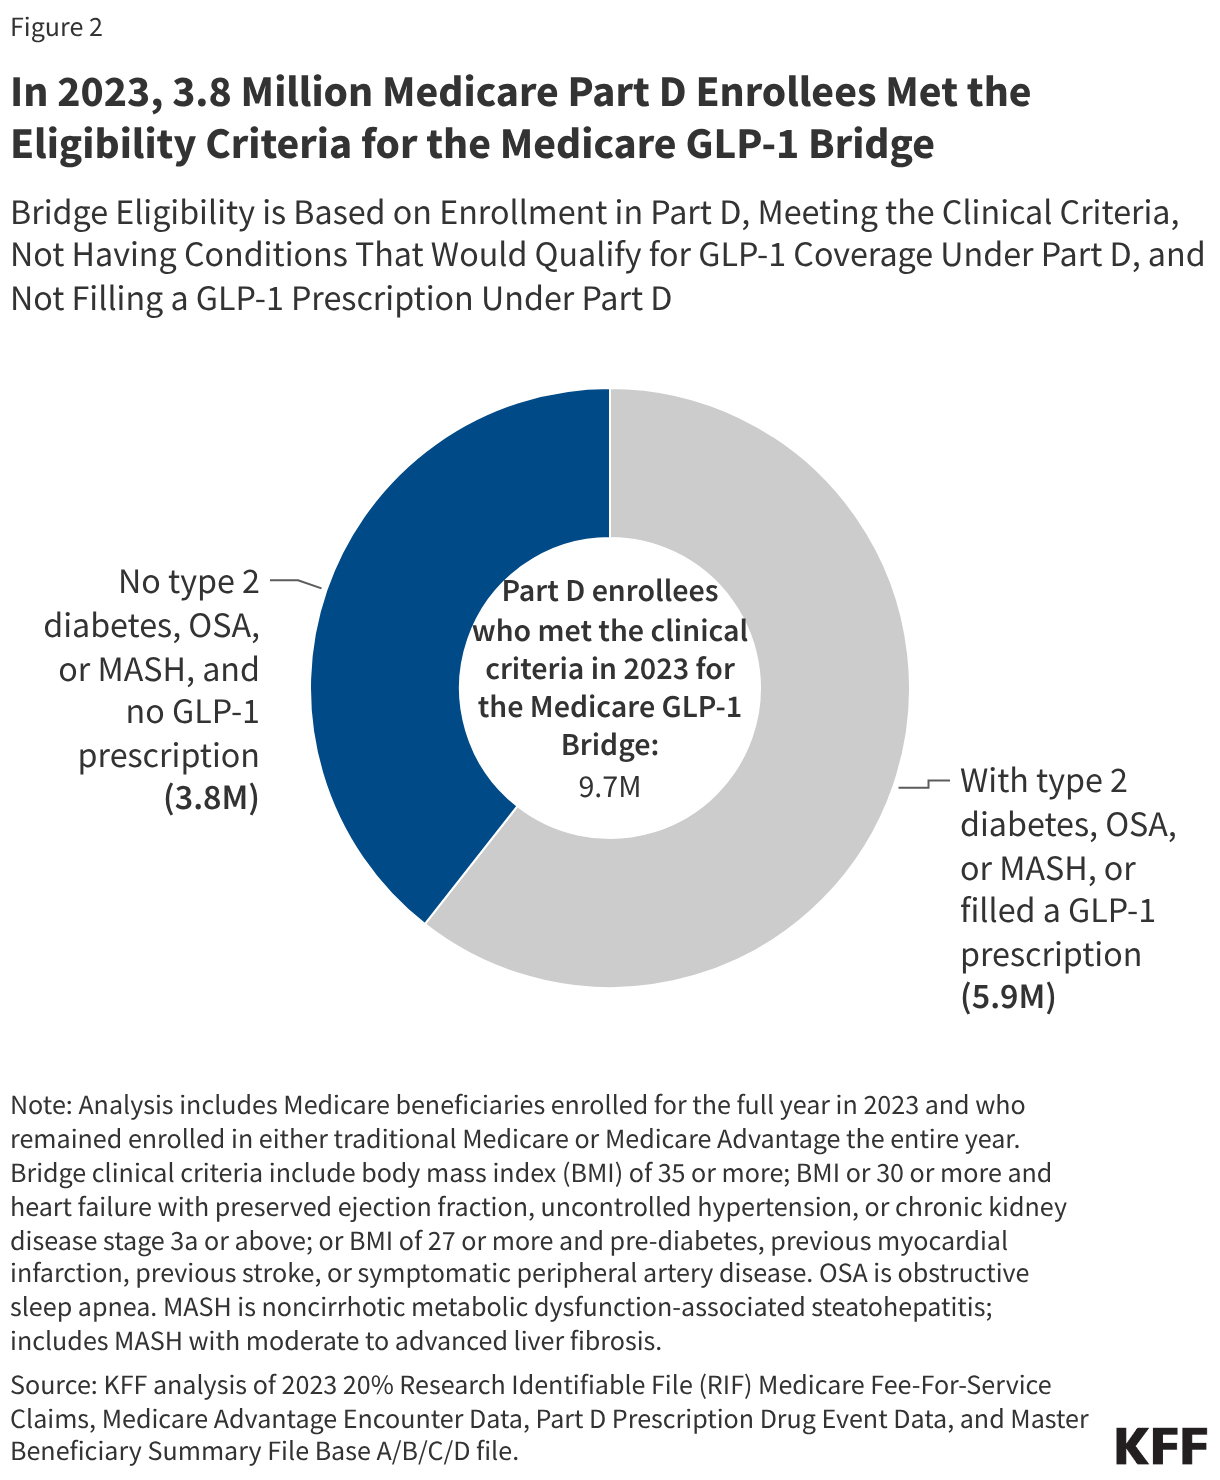
Among the 47.5 million Medicare Part D enrollees in 2023, 9.7 million enrollees met the clinical criteria for the Medicare GLP-1 Bridge in 2023, but less than half of this group—3.8 million (39%)—is estimated to be eligible for Bridge (Figure 2, Table 1). These 3.8 million Part D enrollees met the clinical criteria, did not have a diagnosis of type 2 diabetes, OSA, or MASH, or a GLP-1 Part D-covered prescription in 2023, and could be eligible for the Medicare GLP-1 Bridge, assuming no changes in diagnosis or GLP-1 use in Part D in 2026. This estimate, which includes Part D enrollees in traditional Medicare and Medicare Advantage, represents 8% of Medicare Part D enrollees and 7% of the total population enrolled in Medicare Part A and Part B for the entire year in 2023. The other 5.9 million Part D enrollees met the clinical criteria but also had claims or encounter data recording a diagnosis of type 2 diabetes, OSA, or MASH, and/or had a GLP-1 Part D-covered prescription, either of which would make them ineligible for Bridge.

In 2023, 3.8 Million Medicare Part D Enrollees Met the Eligibility Criteria for the Medicare GLP-1 Bridge (Donut Chart)

The total cost to the federal government of the Medicare GLP-1 Bridge will depend in part on how many beneficiaries are eligible in 2026 and 2027, what share of them participate, how quickly they initiate use under the program after it begins, and how many prescriptions each participating beneficiary fills during the 18-month period. While take-up is uncertain, interest in the program among potentially eligible Medicare beneficiaries is likely to be strong. Based on the estimated 3.8 million Part D enrollees eligible for the Medicare GLP-1 Bridge as of 2023, if 10% to 25% participate in Bridge from when the program launches in July 2026 and fill a prescription each month for the 18-month duration of the program, the cost to Medicare would be $1.3 billion to $3.3 billion (at a net monthly cost of $245 minus the $50 beneficiary copay). Assuming higher participation rates ranging from 50% to 75%, the cost to Medicare would be between $6.7 billion and $10 billion. The ultimate cost to the federal government of the Medicare GLP-1 Bridge will depend on actual participation numbers and adherence during the 18-month program, as well as potential cost offsets from savings that might accrue over time due to beneficiary health improvements from GLP-1 use for weight reduction and weight management.

Estimated Number of Medicare Part D Enrollees Who Met the Clinical Criteria for the Medicare GLP-1 Bridge in 2023 (Table)

Methods

This analysis mapped ICD-10 codes to the clinical criteria specified by CMS for the Medicare GLP-1 Bridge and utilized the 2023 20% Research Identifiable File (RIF) Medicare Fee-For-Service Claims and Medicare Advantage Encounter Data to create condition flags, along with the Part D Prescription Drug Event data to create a flag for GLP-1 use. The 2023 RIF Master Beneficiary Summary File (Base A/B/C/D file) was used to identify individuals to include in the analysis, which were then weighted to produce population estimates. To be included in the analysis of diagnosis with obesity or overweight, an individual was required to have coverage under Parts A and B for all months of 2023, not have switched between traditional Medicare and Medicare Advantage during the year, and remain living for the entire year. To be included in the Bridge eligibility analysis, an individual was required to have coverage for Parts A, B, and D for all months of 2023, not have switched between traditional Medicare and Medicare Advantage during the year, and remain living for the entire year. Individuals were grouped based on their insurance type (traditional Medicare or Medicare Advantage) for 2023. Individuals received a condition flag if they had one or more claims/encounters that matched a respective ICD-10 code mapped onto one of the Bridge clinical criteria in an inpatient, outpatient, carrier, home health, or skilled nursing facility setting in 2023. Individuals received a GLP-1 user flag if they had one or more Part D prescription drug event claims for a GLP-1 medication in 2023.

Diagnoses on Medicare Advantage chart reviews were not included in the creation of the condition flags. This produces a somewhat more conservative estimate of Medicare Advantage enrollees who could be eligible for the Medicare GLP-1 Bridge.

This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

VOLUME 49

KFF Poll Shows Three in Ten Adults Turn to Social Media or AI for Health Information, with Lower-Income Adults More Likely to Cite Cost and Access Barriers as a Reason


Highlights

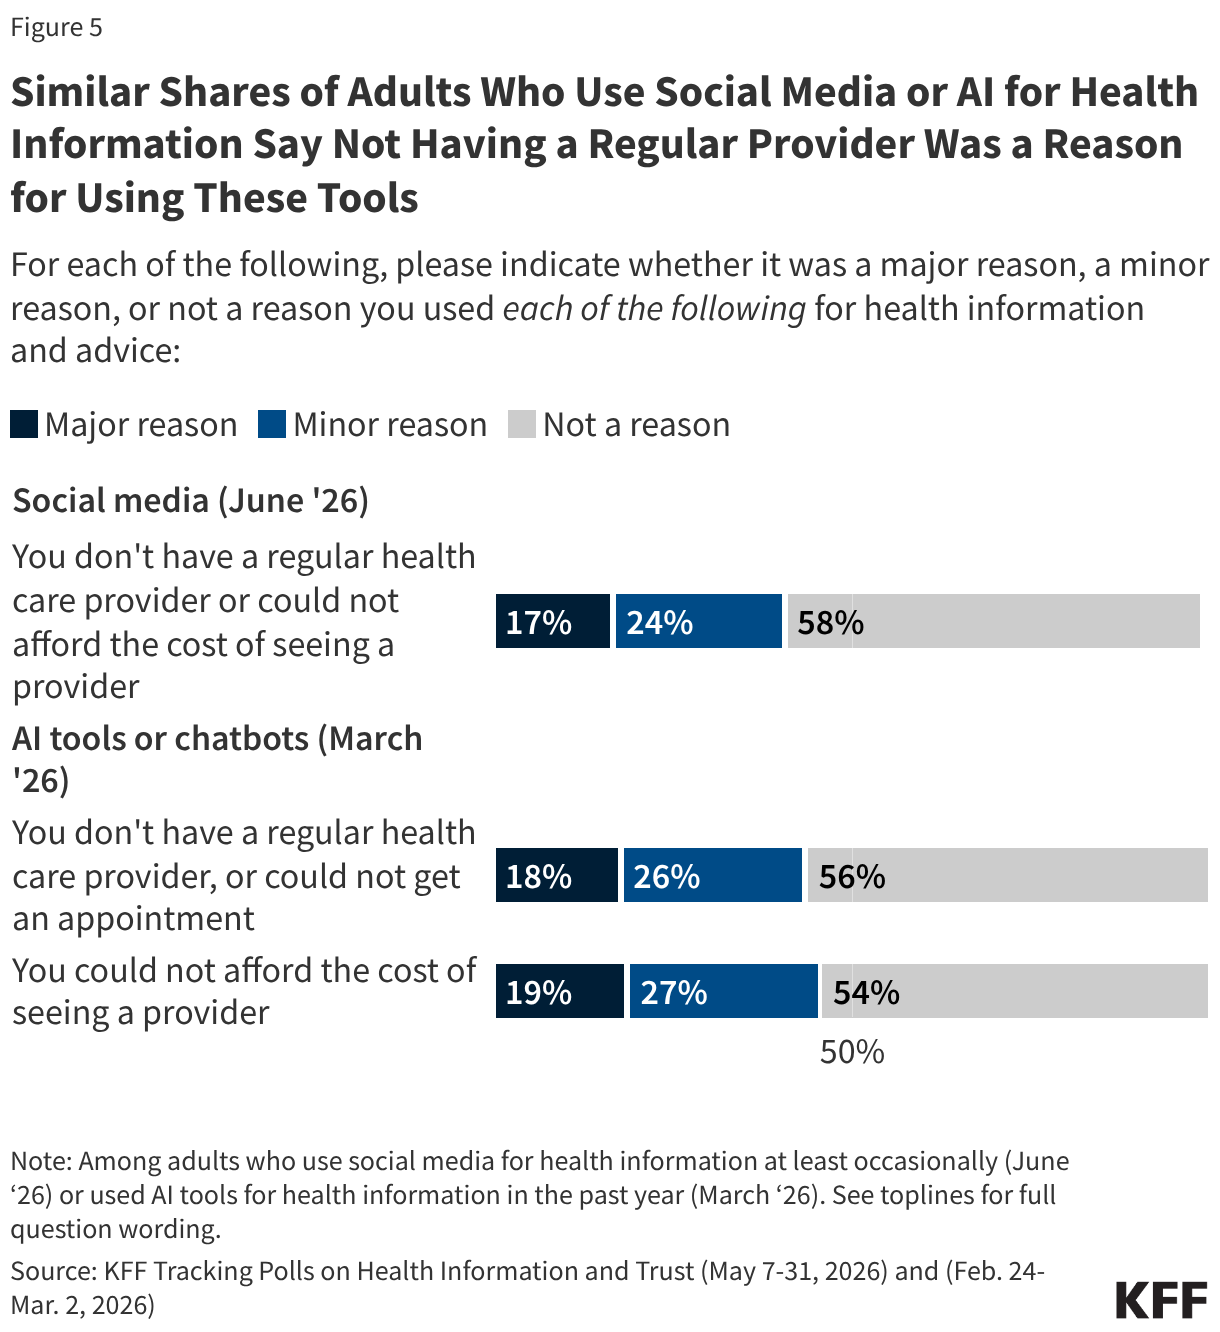
The latest KFF Tracking Poll on Health Information and Trust finds roughly three in ten adults report turning to social media (31%) or AI chatbots (29%) at least monthly for health information and advice. The top reasons people report turning to social media for health advice are wanting to hear from those with similar experiences or a desire for quick information. But nearly one in five say they turned to social media due to difficulties accessing or affording care, similar to the shares who cited access and cost as reasons for turning to AI for health information in a previous KFF poll.  

These findings as well as data from dozens of past KFF polls can also be found on KFF’s Health Information and Trust Polling Dashboard.  


KFF Poll Shows Three in Ten Adults Regularly Turn to Social Media or AI For Health Advice, With Similar Shares of Social Media and AI Users Citing Barriers to Accessing Care as a Reason for Using These Platforms

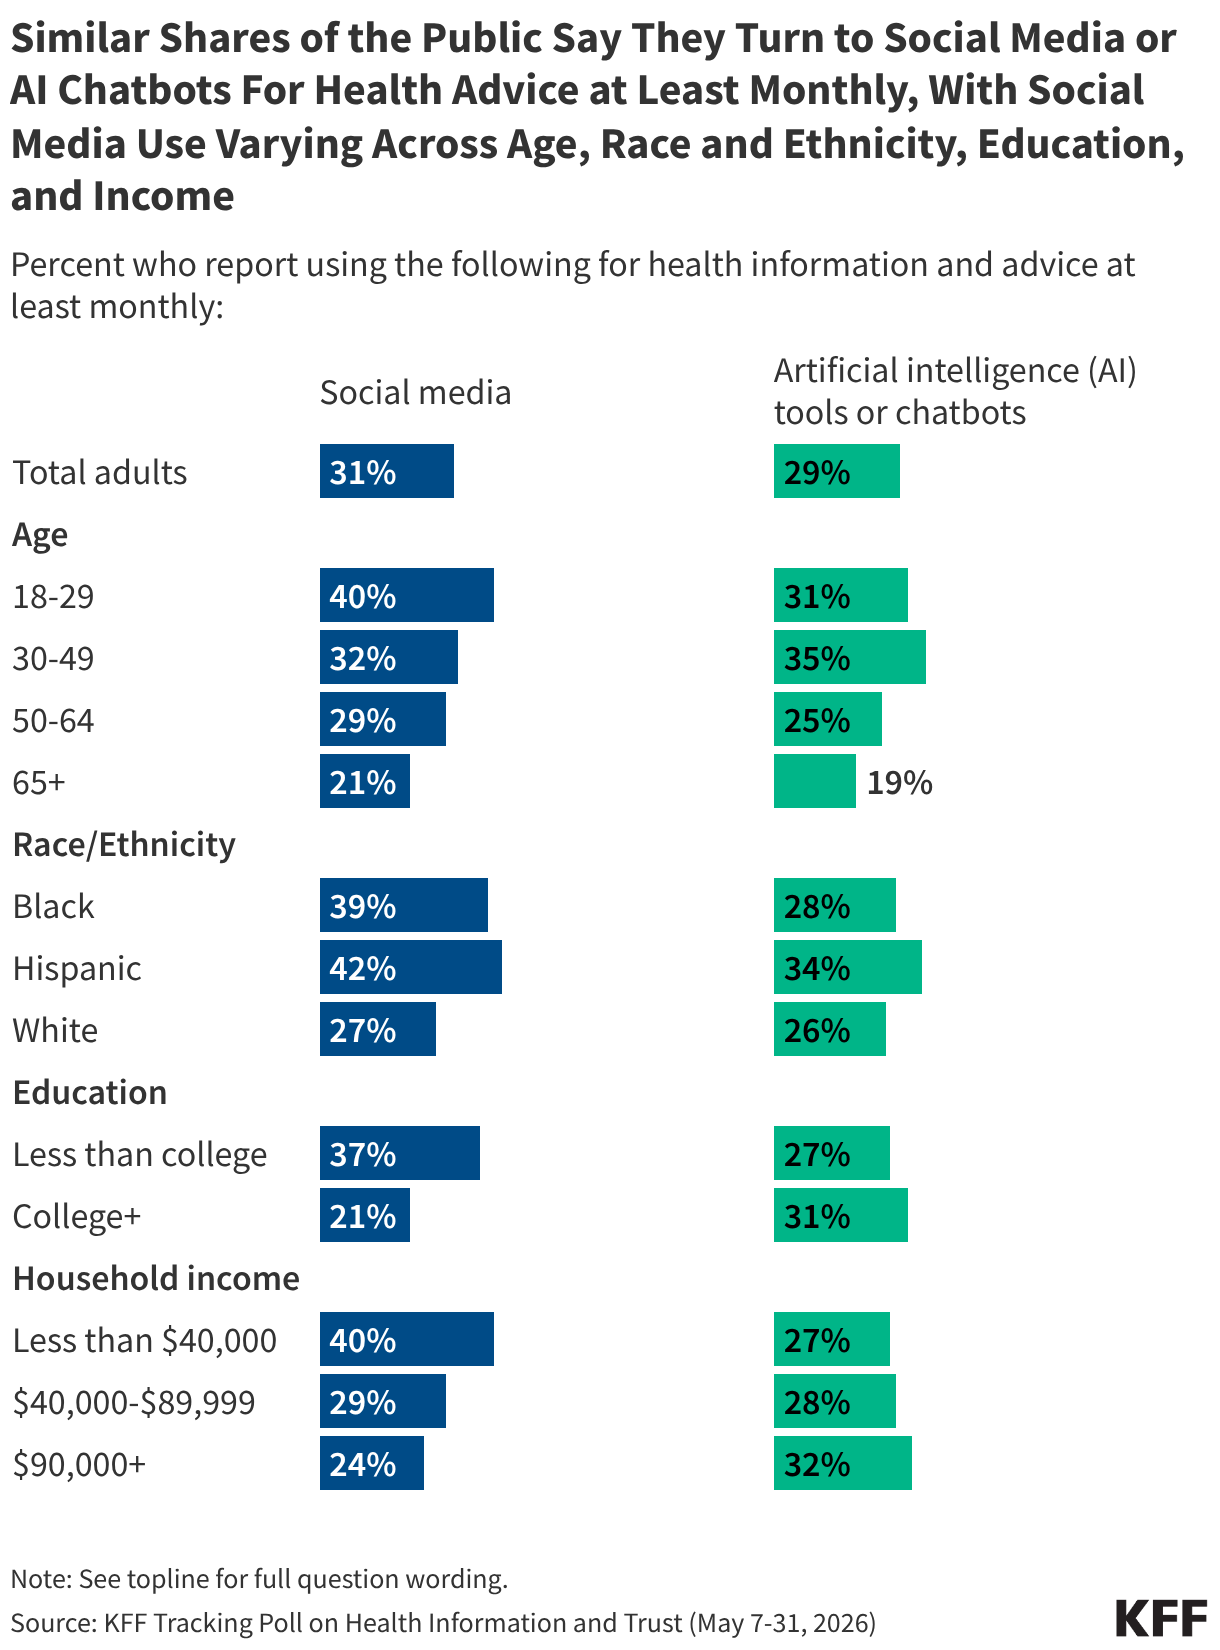
KFF’s latest Tracking Poll on Health Information and Trust examines the public’s use of social media and AI for health information. Overall, three in ten (31%) adults say they use social media at least monthly for health information and advice, similar to the share (29%) who say they use artificial intelligence (AI) tools or chatbots at least monthly for health. Larger shares of adults under 30, Black and Hispanic adults, those without a college degree, and those with lower incomes say they turn to social media for health information at least monthly. 

Split bar chart showing the percent of people who report using social media or AI tools for health information and advice at least monthly. Results by total adults, age, race/ethnicity, education, and household income.

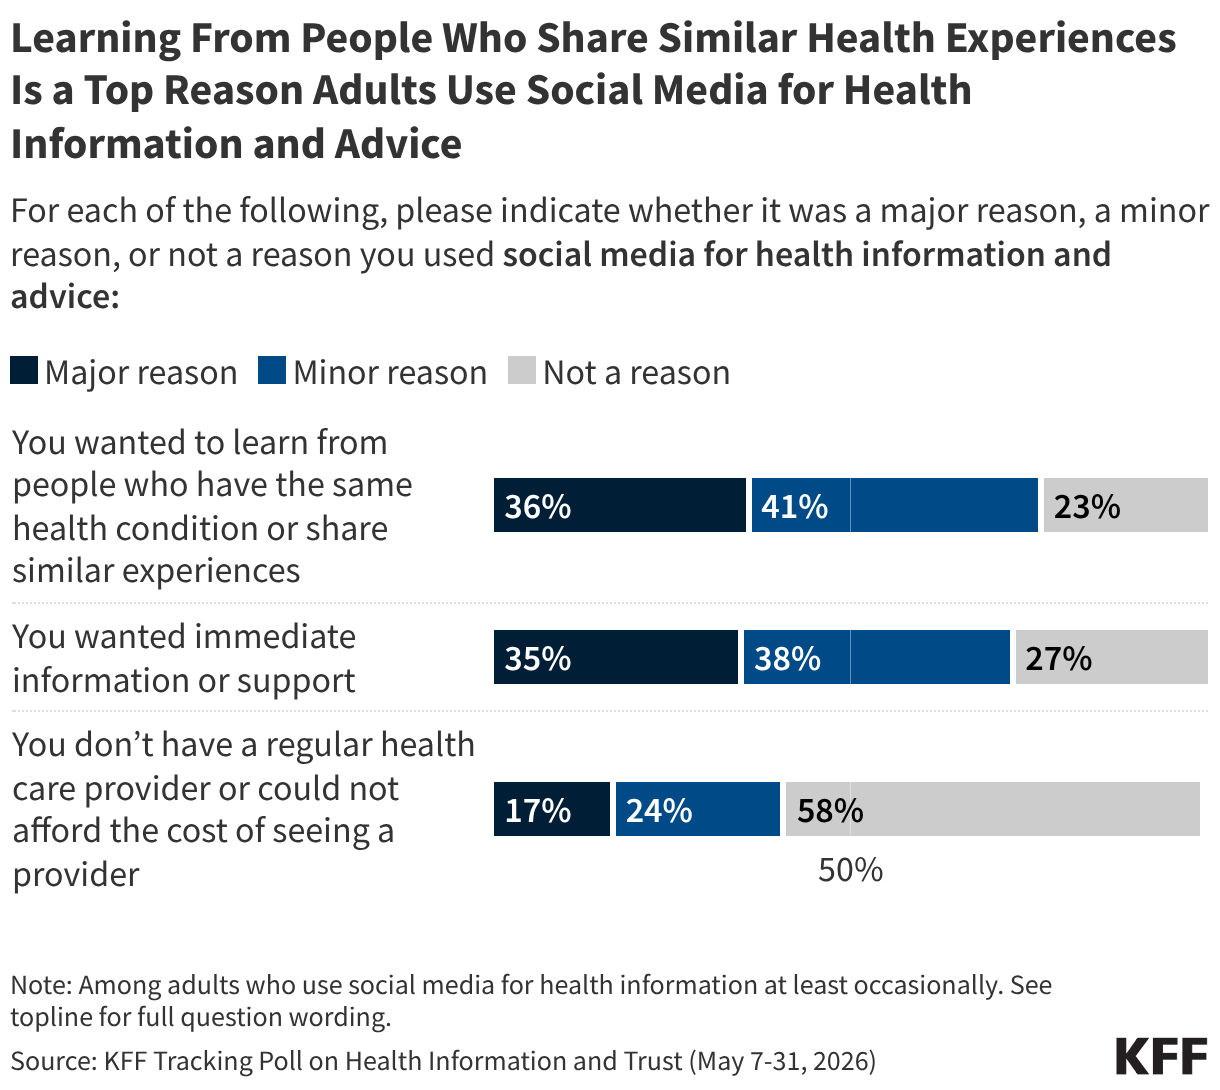
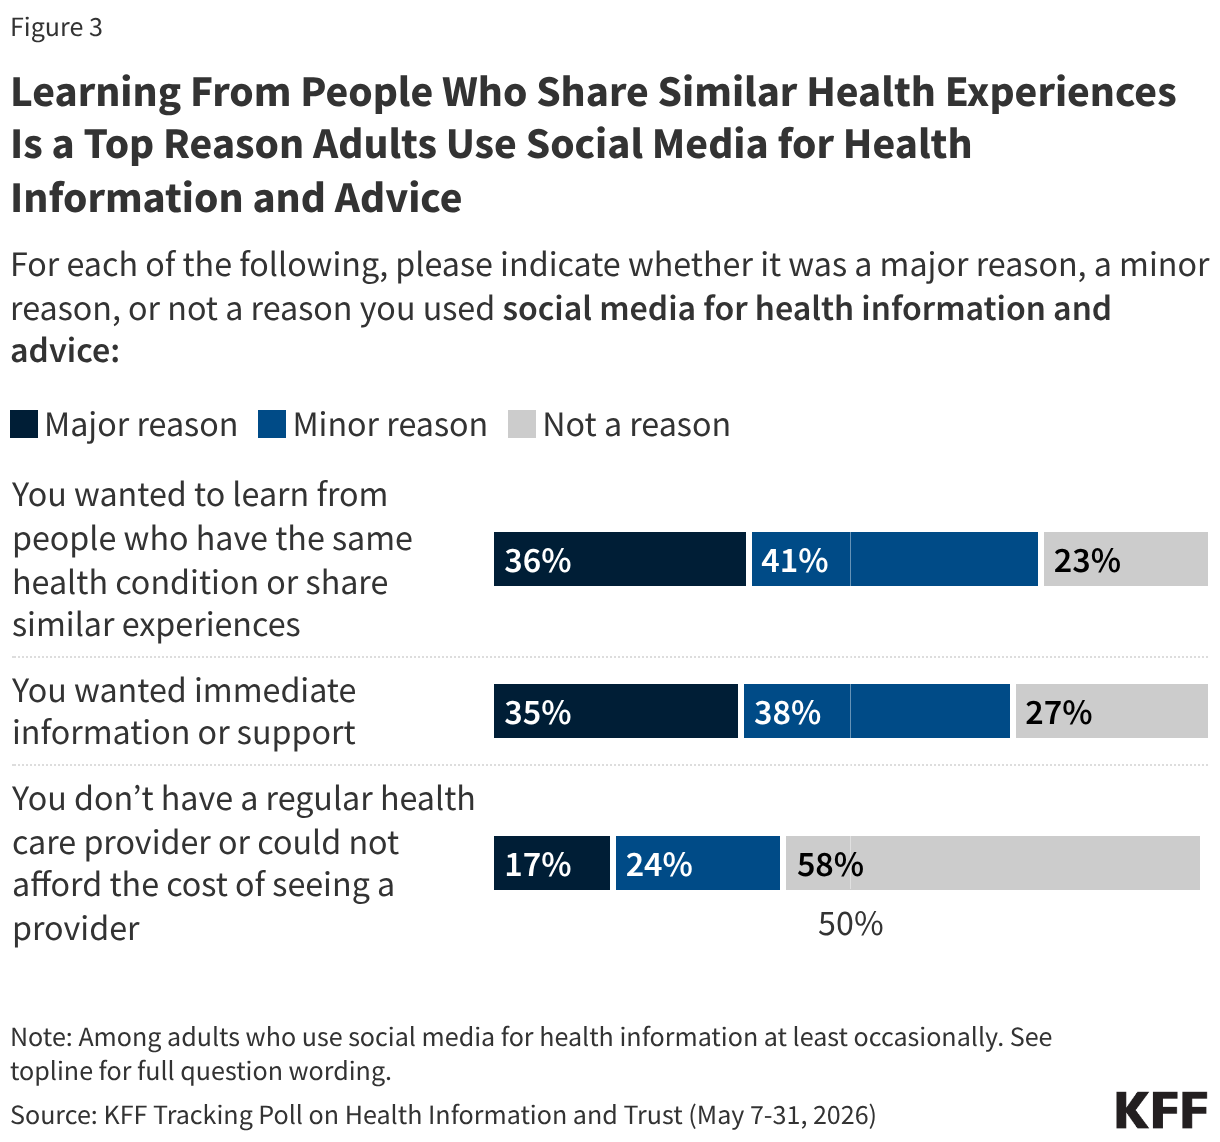
Among people who use social media for health information at least occasionally, over a third say a “major reason” they did so was to learn from others with similar experiences or conditions (36%) or because they wanted immediate information or support (35%). A smaller share of users (17%) say a “major reason” they relied on social media was because they don’t have a health care provider or couldn’t afford to see one.

Stacked bar chart showing the percent of people who selected wanting to learn from others, wanting immediate information, and not having a regular health care provider as a reason for using social media to find health information and advice.

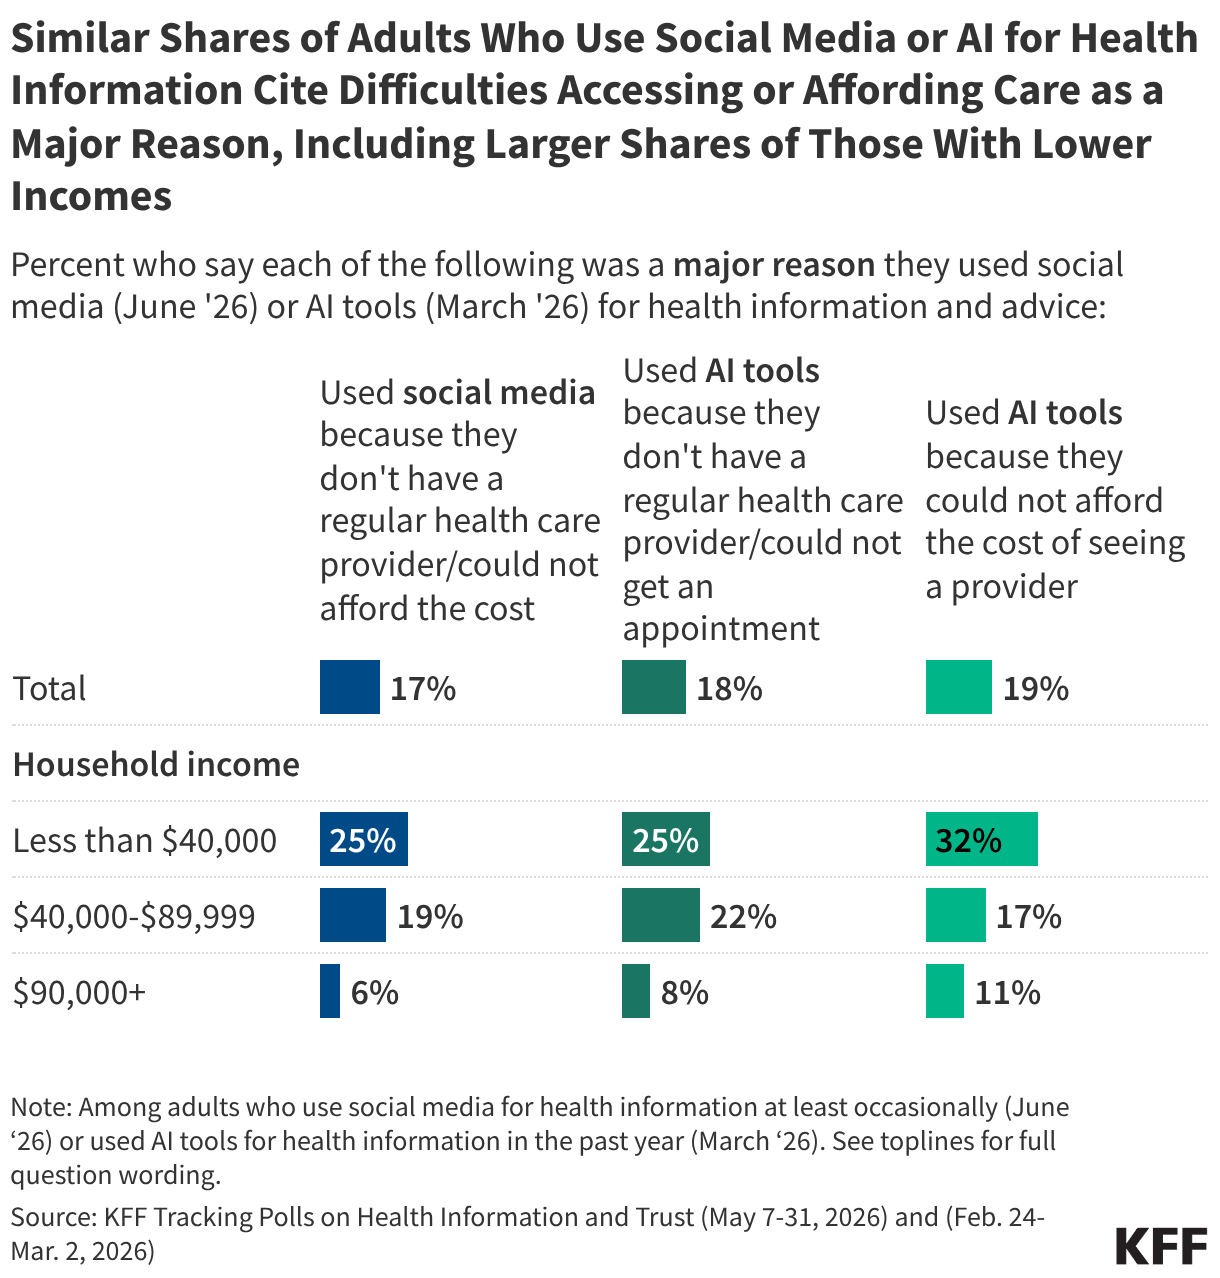
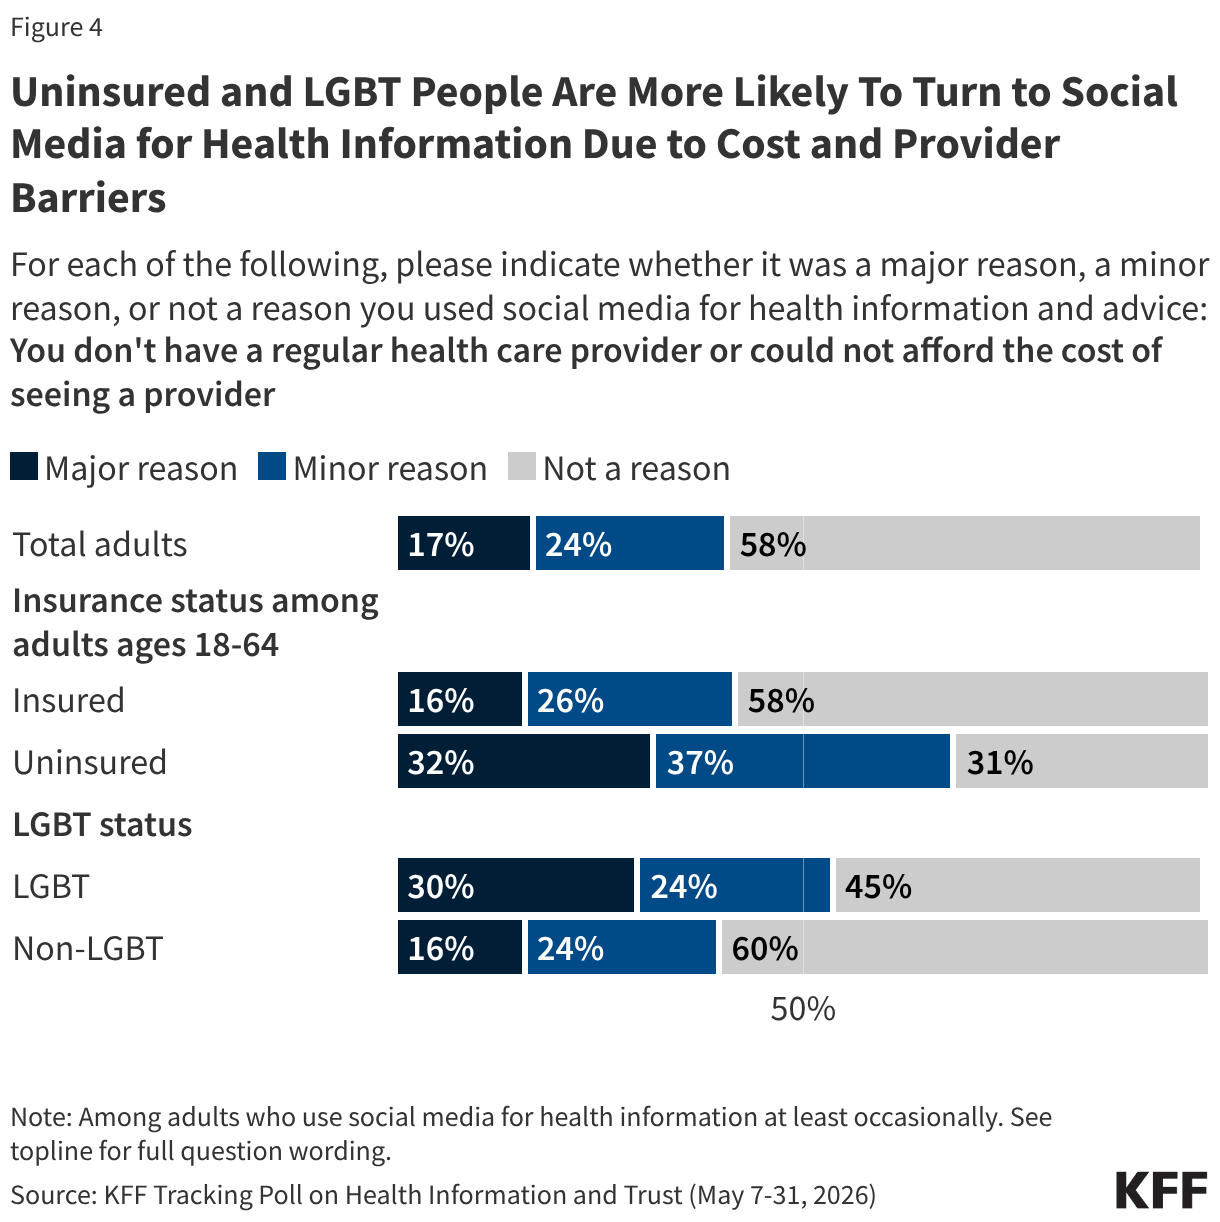
While cost and access problems may not be the top reason people turn to either social media or AI for health information, nearly one in five users are turning to each of these mediums for these reasons, including even higher shares among those with lower incomes. Among adults who use social media for health, this reason is also more commonly cited among uninsured adults (32%) and some groups that have historically had a harder time accessing health care, including Hispanic adults (29%) and LGBT adults (30%). 

Similar Shares of Adults Who Use Social Media or AI for Health Information Cite Difficulties Accessing or Affording Care as a Major Reason, Including Larger Shares of Those With Lower Incomes (Split Bars)

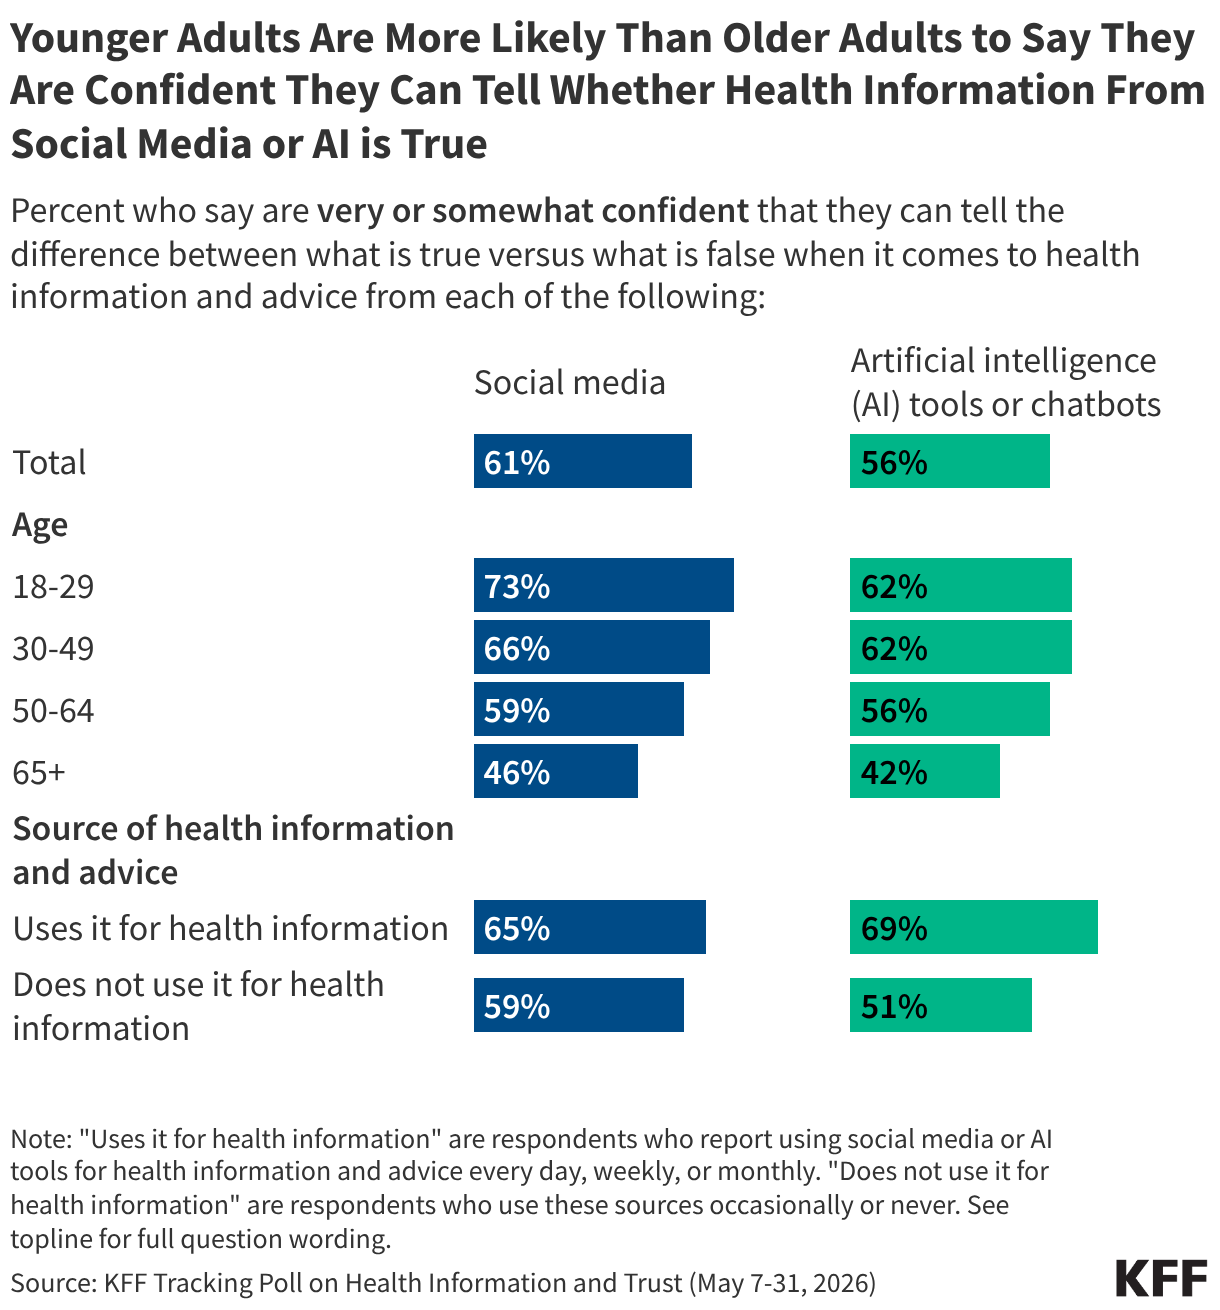
While a slim majority of adults express confidence in their ability to tell whether health information from social media or AI tools is true or not, about four in ten lack confidence in this regard. Adults who use social media and AI for health information are more likely than those who don’t to express confidence in their ability to discern whether health information on these platforms is true or not, as are younger adults compared to older adults.

Grouped bar chart showing the percentage of adults who say they are very or somewhat confident they can tell true from false health information from social media and from AI tools or chatbots, broken down by total adults, age group, and whether they use each source for health information.

AI & Emerging Tech

Understanding the Role of AI in Spreading and Creating Faulty Research

  • A correspondence published in The Lancet in May identified more than 4,000 fabricated references across nearly 2.5 million biomedical papers published between 2023 and early 2026. Researchers found that papers containing at least one fabricated citation became substantially more common during the study period, rising from roughly one in 2,800 papers in 2023 to one in 277 papers in early 2026. Many of the fabricated references appeared legitimate, citing real researchers, plausible publication years, and topic-specific article titles, but pointed to studies that did not exist.
  • The authors note that large language models (LLMs) are known to generate fabricated citations that appear authentic, and that the sharp rise in fabricated references coincided with the period following widespread adoption of generative AI tools. While the study could not determine what caused the increase, researchers note that fabricated references can emerge through multiple pathways, including AI-generated citations, paper mills, and other forms of research misconduct.

Here’s the big picture:

  • AI systems can amplify inaccurate or fabricated information. Large language models sometimes generate information that sounds plausible but is unsupported or entirely false, a phenomenon often referred to as "hallucination." A 2025 study found that when fictional medical terms were included in health questions, chatbots elaborated on them in nearly two-thirds of cases, generating explanations and treatments for conditions that do not exist. Researchers demonstrated a similar dynamic in an experiment involving a fictional skin condition called "bixonimania." After uploading fake papers about the condition to a preprint server, they found that several major AI chatbots described the made-up disorder as real and, in some cases, recommended medical care. The fabricated papers were later cited in a peer-reviewed article before being retracted.
  • AI systems increasingly interact with scientific literature that contain fraudulent or unreliable research. Researchers have documented the growing presence of "paper mills," operations that produce and sell fraudulent academic manuscripts. A study in BMJ found that nearly 10% of cancer research papers showed signs of paper mill involvement, with the proportion increasing over time. Because AI systems are trained on large volumes of publicly available content, including scientific literature, concerns have emerged that low-quality or fraudulent research may influence the information these systems retrieve, summarize, or generate. Some research has shown that even when fraudulent papers make up just 0.01% of an AI system's training data, they can contribute to errors in as many as 10% of responses.
  • Generative AI is also lowering barriers to producing convincing scientific content. Researchers have identified AI-generated manuscripts circulating through academic publishing and scholarly databases, sometimes without disclosure of AI assistance. The ability to rapidly generate text, references, and literature reviews raises concerns that AI could accelerate the production of papers that appear credible but contain errors, unsupported claims, or fabricated citations. As a result, some researchers and publishers are calling for stronger screening, reference verification, and disclosure requirements throughout the publication process.

Why This Matters: AI is increasingly involved at multiple stages of the scientific information ecosystem, from generating content and citations to retrieving and summarizing published research. As fabricated references, fraudulent papers, and other forms of low-quality research become harder to distinguish from legitimate scholarship, weaknesses in one part of the system can affect others. New efforts to detect paper mills, verify references, and improve AI reliability are underway, but people are already using AI tools to answer health questions.


What We’re Watching

A Closer Look at the State Level: New Jersey Poll Finds Broad Concern About Misinformation, Alongside Use of Search and Social Platforms

A Rutgers-Eagleton Poll commissioned by the New Jersey Civic Information Consortium found that concerns about misinformation are widespread among New Jersey voters, with 60% describing the spread of false or misleading information as a "very big problem" and another 22% calling it a "moderately big problem." The survey also found that New Jerseyans frequently rely on digital channels for news, including search engines (77%), friends and family (75%), and national news outlets (71%). At the same time, about one-third of voters (34%) said local news coverage in their area has decreased over the past five years. Rutgers researchers noted that concern about misinformation was shared across demographic and political groups, suggesting a rare point of bipartisan agreement.

Why This Matters: The findings are consistent with 2023 KFF polling among the general public, which found that a vast majority of adults (83%) say the spread of false and inaccurate information in the United States is a “major problem.” At the same time, the Rutgers-Eagleton survey sheds light on the role that search engines, social networks, and interpersonal connections play in how people access information and evaluate its credibility.

About The Health Information and Trust Initiative: the Health Information and Trust Initiative is a KFF program aimed at tracking health misinformation in the U.S., analyzing its impact on the American people, and mobilizing media to address the problem. Our goal is to be of service to everyone working on health misinformation, strengthen efforts to counter misinformation, and build trust. 


View all KFF Monitors

The Monitor is a report from KFF’s Health Information and Trust initiative that focuses on recent developments in health information. It’s free and published twice a month.

Sign up to receive KFF Monitor
email updates


Support for the Health Information and Trust initiative is provided by the Robert Wood Johnson Foundation (RWJF). The views expressed do not necessarily reflect the views of RWJF and KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities. The data shared in the Monitor is sourced through media monitoring research conducted by KFF.

Medicaid Program Integrity: Tracking State-Specific and Nationwide Federal Action

Published: Jun 25, 2026

The Trump Administration and Congress continue to focus on rooting out fraud, waste, and abuse in federal programs, including Medicaid. Those efforts include 50-state initiatives and targeted actions that focus on issues in specific states. Given the quickly evolving Medicaid program integrity landscape, this page tracks emerging developments in the federal government’s approach to program integrity in Medicaid, along with the implications of those actions for different states. For more detailed analyses and context, see ‘Related Resources’ in Section 2.

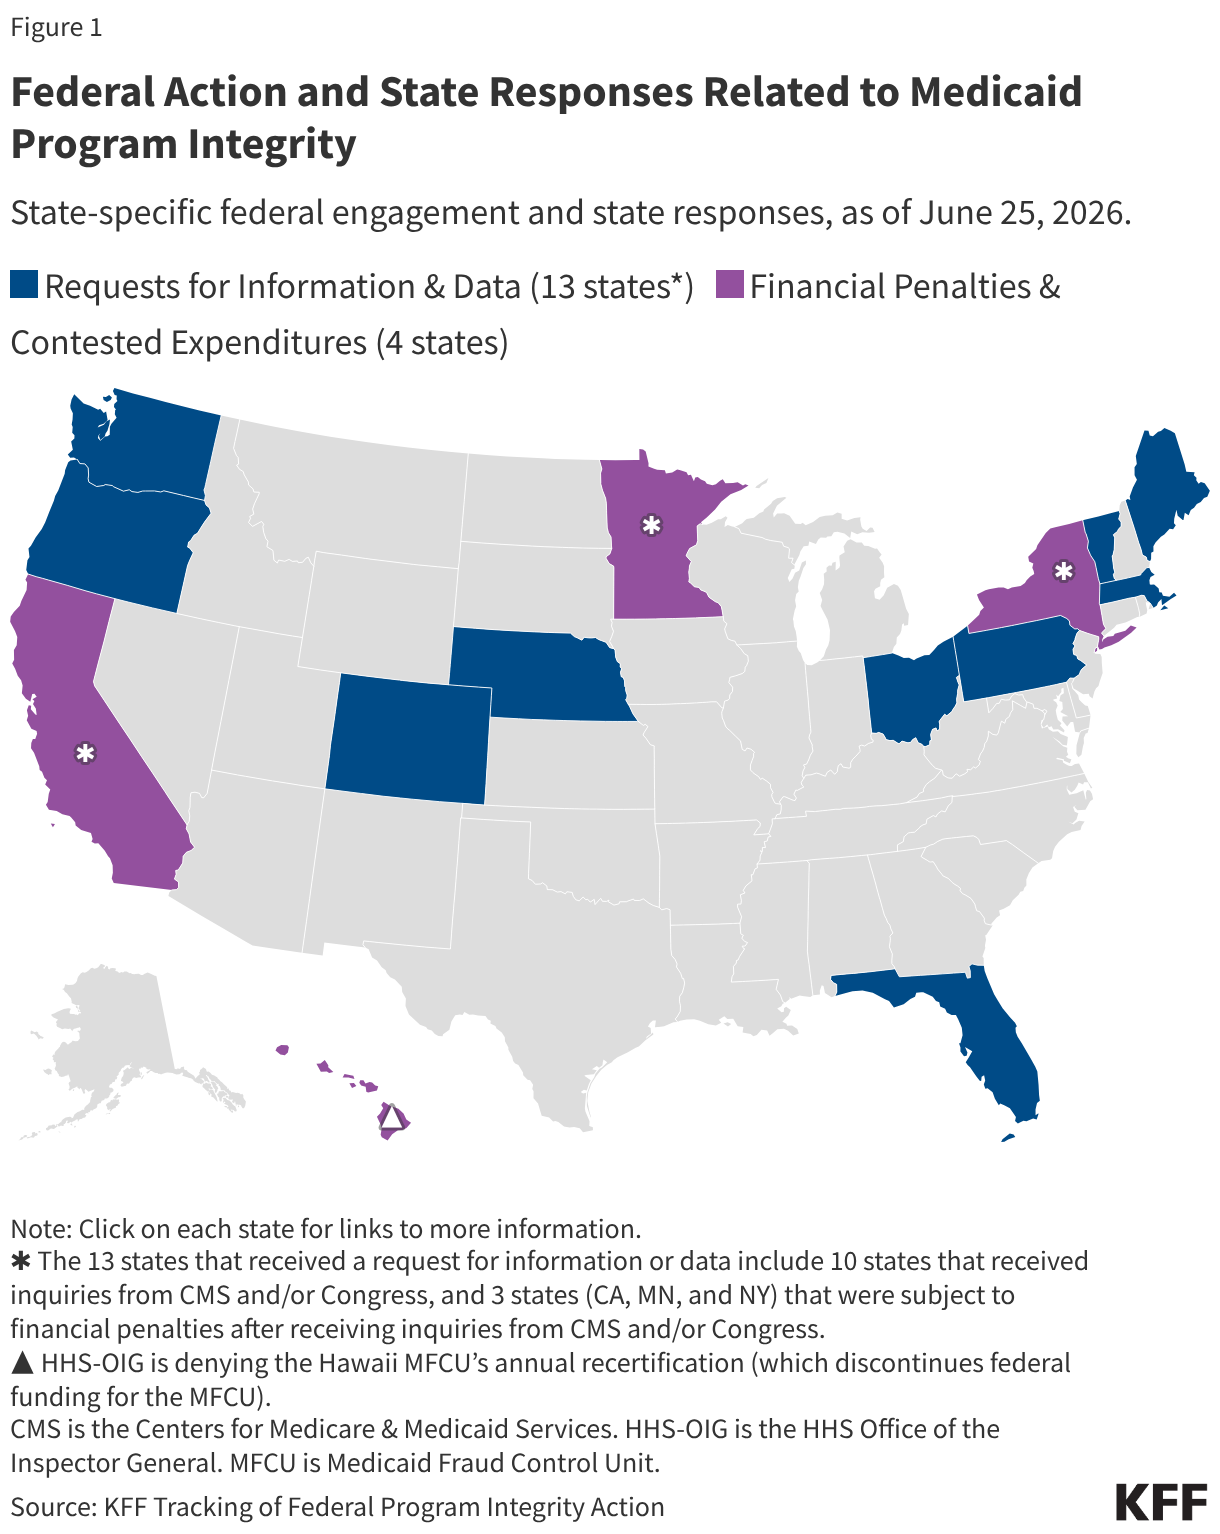
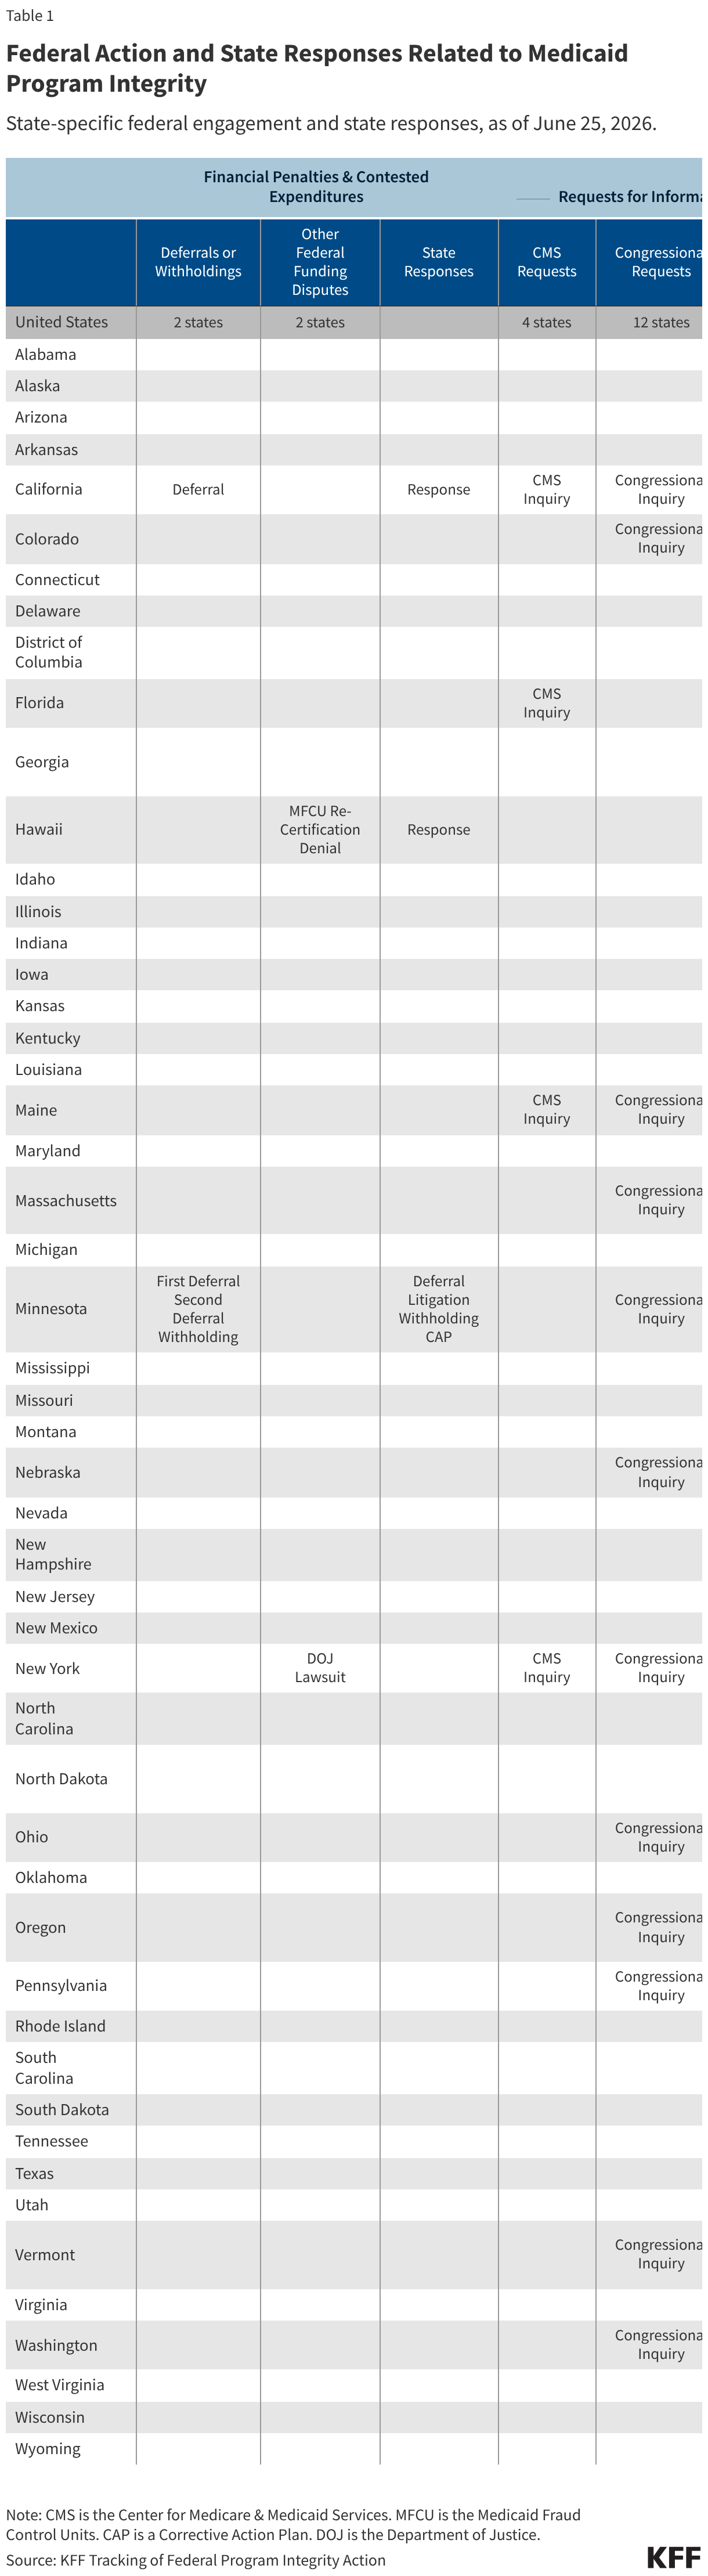
This page tracks the federal government’s 50-state initiatives and targeted actions focused on Medicaid program integrity (Figure 1 and Table 1). The map and tracker include federal actions towards states and exclude actions towards providers (such as those governing providers’ ability to participate in Medicaid and civil or criminal charges).

The following federal actions are included when materials are publicly available, along with states’ publicly available responses:

  • Financial penalties and contested expenditures including:
    • Notices of potential or actual withholding, deferrals, or disallowances of federal funding expressly tied to program integrity concerns; and
    • Other federal Medicaid funding in dispute (e.g., Health and Human Services (HHS)-Office of the Inspector General (OIG) funding for Medicaid Fraud Control Units or Department of Justice (DOJ)-contested state Medicaid program expenses).
  • Requests for state information and state responses, including formal inquiries, probes, or other materials that investigate specific state Medicaid programs or require states to respond with new information or an action plan.

The figure and table exclude the following actions:

  • Routine deferrals/disallowances (i.e., deferrals/disallowances only for longstanding disputed Medicaid claims and/or are not identified by CMS as expressly tied to concerns about fraud/waste/abuse);
  • HHS-OIG audits that are initiated as part of planned work and are more narrow or targeted in scope, and/or are not expressly tied to broader concerns about fraud/waste/abuse;
  • Routine DOJ proceedings (i.e., proceedings which target specific instances of fraud/waste/abuse against a Medicaid program but do not name a state Medicaid official as party to the case nor tie state claims for federal Medicaid funds to a case outcome); and
  • State or federal actions that do not have publicly available documentation (i.e., actions that may be referenced or announced in reporting or on social media but without documentation from federal or state governments).
Federal Action and State Responses Related to Medicaid Program Integrity (Choropleth map)
Federal Action and State Responses Related to Medicaid Program Integrity (Table)

Key Facts About Medicare Spending Trends and Projections from the 2026 Medicare Trustees Report

Published: Jun 24, 2026

On June 9, 2026, the Medicare Trustees issued the annual report on the financial status of the Medicare program for 2026. The Trustees highlighted that the Medicare Part A trust fund is projected to be depleted in 2033, the same year but one quarter earlier than last year’s projection. In addition to discussing the status of the Part A trust fund, the report also provides substantial additional details on federal spending for Medicare Part B and Part D benefits, the distribution of spending for traditional Medicare and Medicare Advantage, and revenue sources for Medicare, along with updated spending and revenue projections and a detailed discussion of factors that have contributed to changes in the program’s financial outlook. This brief provides an overview of key trends in Medicare spending and spending growth, as well as the impact of these trends on out-of-pocket costs for Medicare beneficiaries and Medicare program solvency, as projected by the Medicare Trustees.

Physician Services and Other Outpatient Services Account for Roughly Half of Total Medicare Benefits Spending

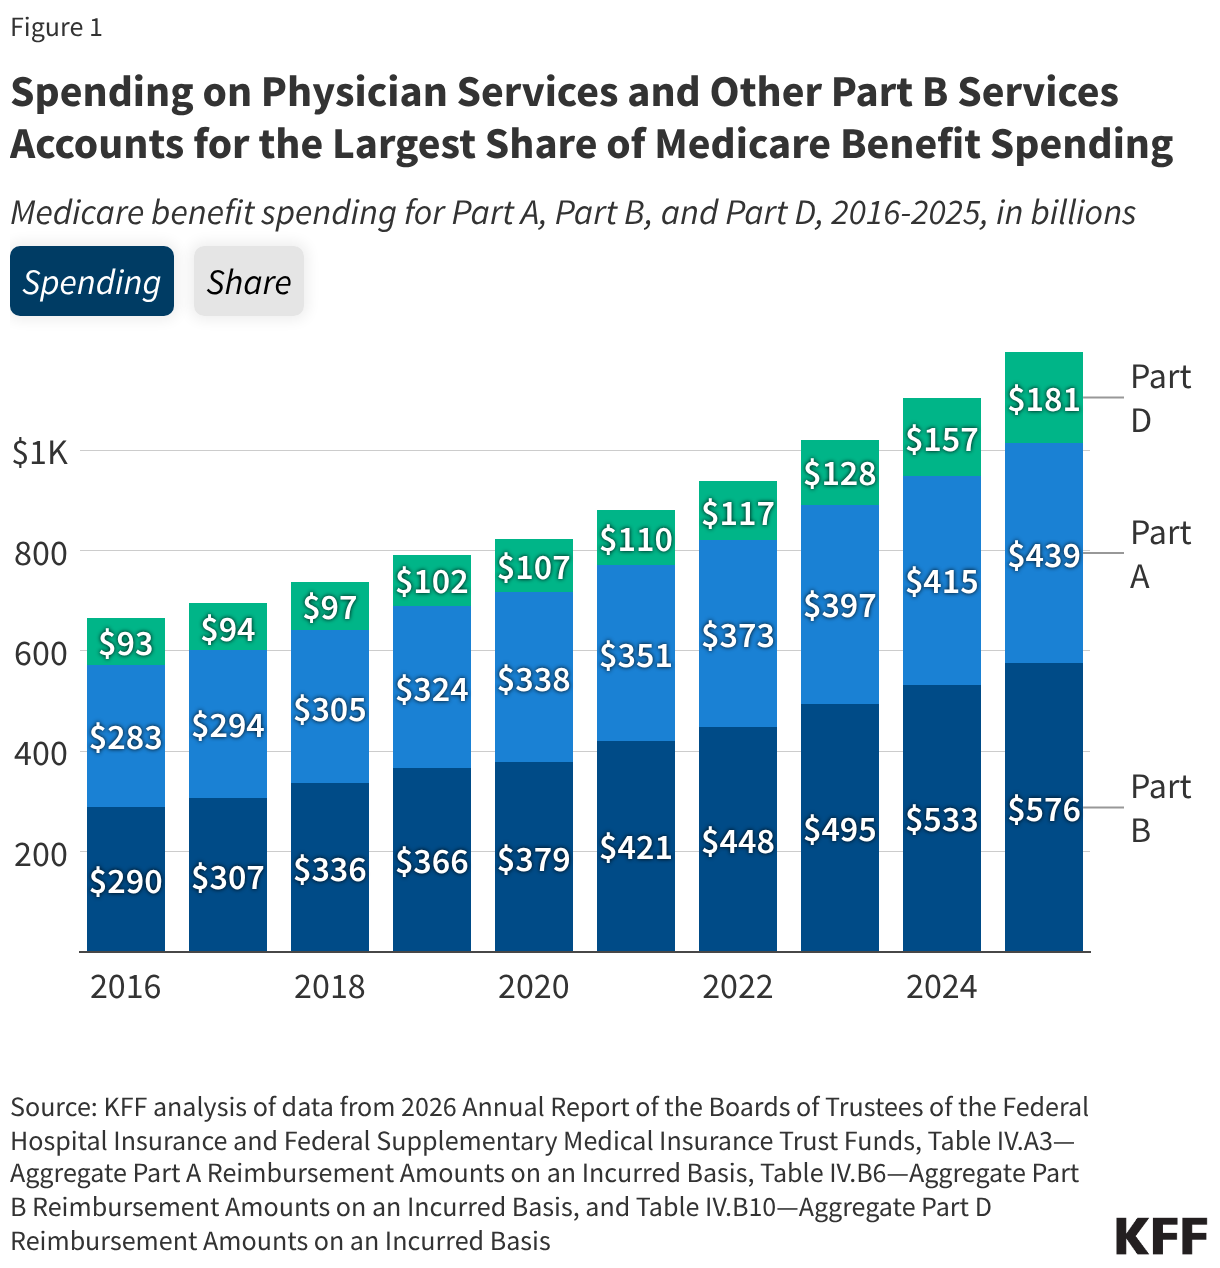
In 2025, Medicare benefit payments totaled $1.2 trillion, up from $666 billion a decade earlier (Figure 1). Spending on Part B services (including physician services, outpatient services, and physician-administered drugs) accounts for the largest share of Medicare benefit spending (48% in 2025), as it has since 2015. In contrast, spending on Part A services (including inpatient hospital services, skilled nursing facility services, and hospice care) has declined as a share of Medicare benefit spending (from 43% in 2016 to 37% in 2025). Over time, this decline has been driven in part by a shift of some services from inpatient to outpatient settings reflecting changes in practice patterns, along with increases in spending on services covered under Part B, including high-cost physician-administered drugs. Spending on Part D prescription drugs has accounted for a relatively constant share of Medicare benefit spending for much of the past decade (12-13%) but rose to 15% in 2025 and is projected to continue growing in the coming years.

Spending on Physician Services and Other Part B Services Accounts for the Largest Share of Medicare Benefit Spending (Stacked column chart)

Spending on Part A and Part B Benefits in Traditional Medicare Was $481 Billion in 2025

Looking at spending by type of service in traditional Medicare, the single largest category of benefit spending in 2025 was for inpatient hospital services covered under Part A (spending by type of service for Medicare Advantage enrollees is unavailable). Although a relatively small share of beneficiaries use inpatient hospital services, these services accounted for roughly one-third of total benefit spending in traditional Medicare ($159 billion or 33%), followed by outpatient hospital services covered under Part B ($76 billion or 16%) (Figure 2). This means that combined spending on hospital services (both inpatient and outpatient) accounted for nearly half of spending on Part A and Part B benefits in traditional Medicare in 2025. Services covered under the Medicare Part B physician fee schedule accounted for $71 billion (15%), and the remaining $174 billion (36%) consisted of payments for all other Part A and Part B services, including physician-administered drugs (8%), skilled nursing facility services (6%), and hospice care (6%), among others.

Figure 2

Spending on the Medicare Part D Prescription Drug Benefit is Projected to be Significantly Higher Over the Coming Decade Compared to Last Year’s Projections

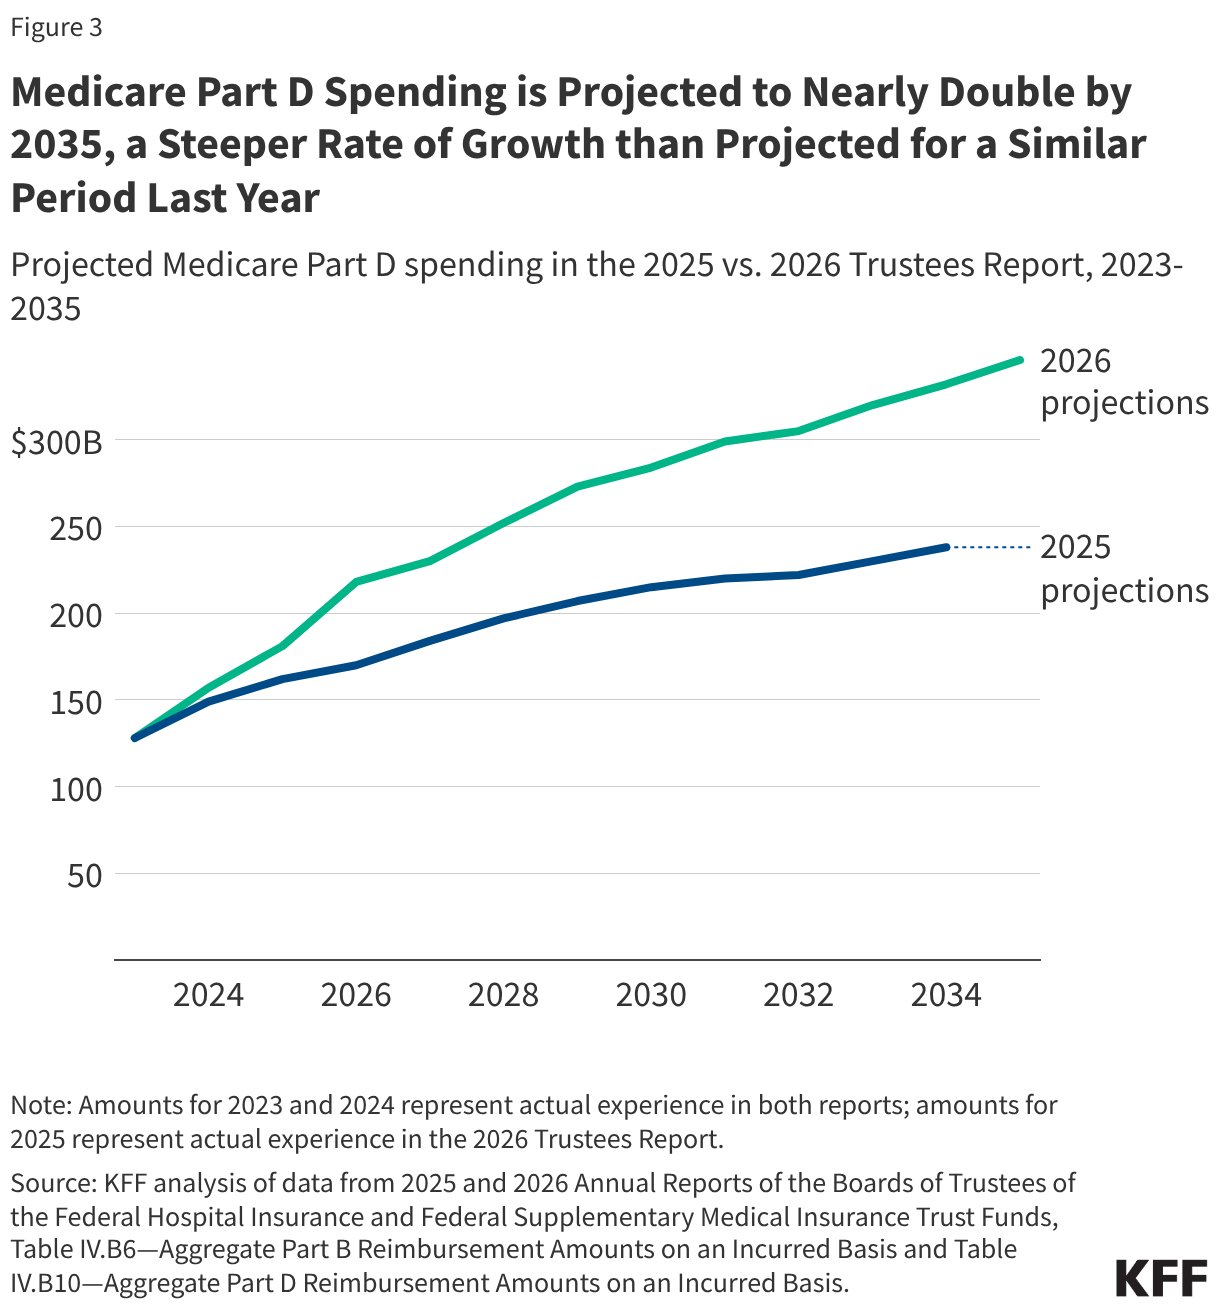
The Medicare Trustees currently project that Medicare Part D spending will nearly double from 2025 ($181 billion) to 2035 ($346 billion), representing an average annual growth rate of 6.7% compared to the 4.8% that was projected for a similar period last year (Figure 3). The Trustees indicate that higher spending projections for Part D in the 2026 report are due to increased use of GLP-1s and other high-cost specialty drugs. The Trustees also point to other factors that have contributed to changes in Part D spending in recent years, including the pharmacy price concessions policy that lowers point-of-sale prices for beneficiaries but reduces rebate revenue to Part D plans, which leads to higher federal Part D spending; the exemption of more orphan drugs from drug price negotiation in the 2025 budget reconciliation bill (H.R. 1), which will lower federal savings from negotiation; and the redesigned Part D benefit that improved the generosity of coverage while shifting more liability onto plans and increased the level of federal subsidies for coverage. These higher spending trends are offset somewhat by the effect of drug price negotiations and inflation rebates established by the Inflation Reduction Act.

Medicare Part D Spending is Projected to Nearly Double by 2035, a Steeper Rate of Growth than Projected for a Similar Period Last Year (Line chart)

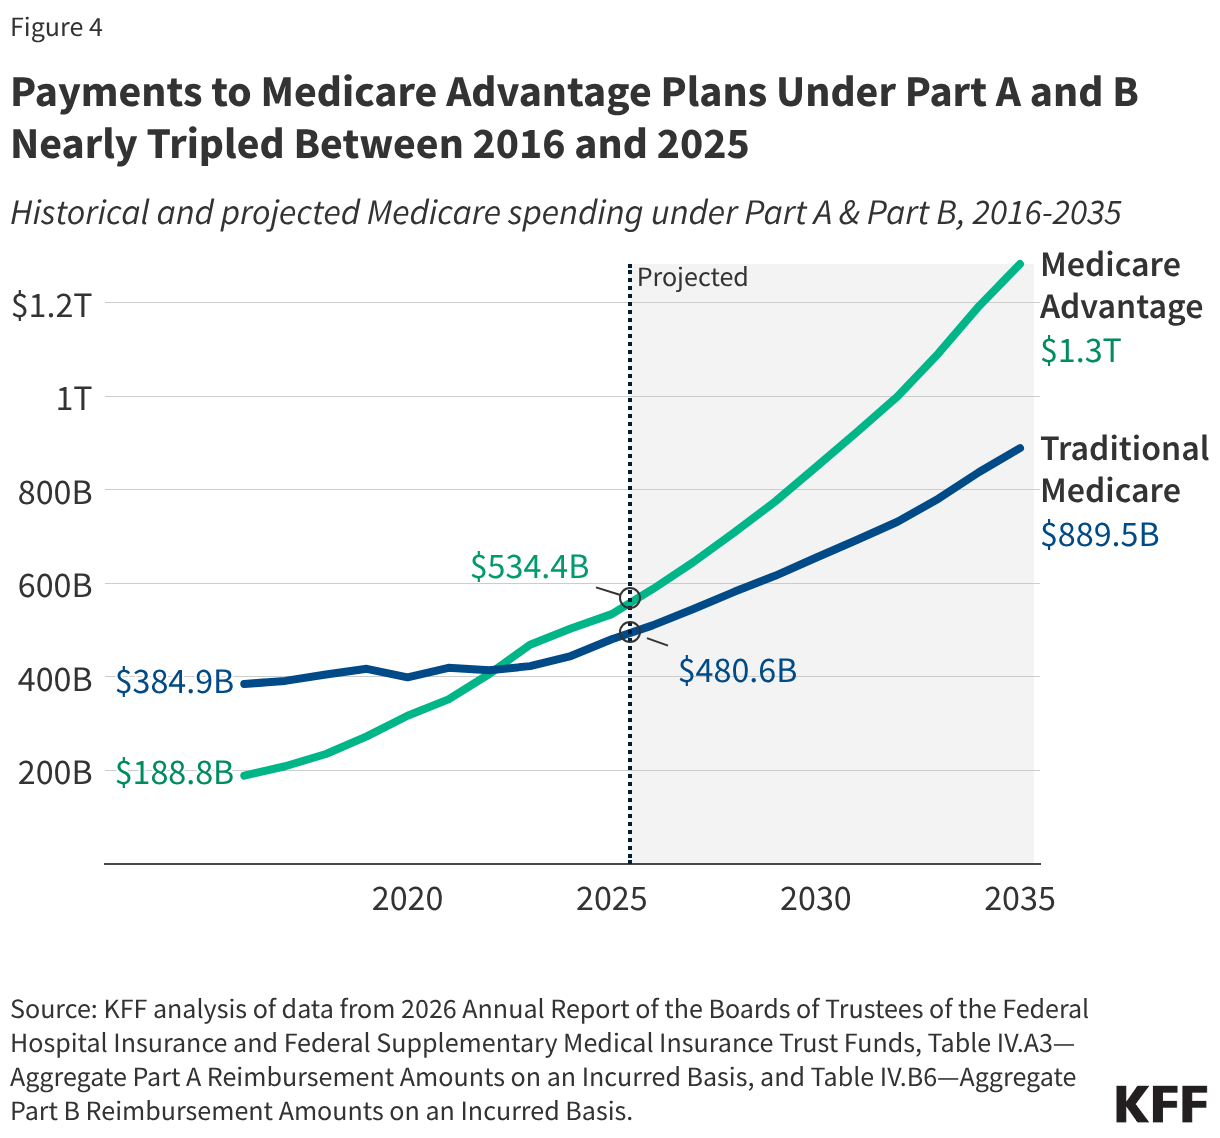
Spending on Medicare Advantage was $534 Billion in 2025, Over Half (53%) of Total Medicare Program Spending

Payments to Medicare Advantage plans under Medicare Part A and Part B nearly tripled as a share of total Part A and Part B spending between 2016 and 2025 (from $189 billion to $534 billion), including payments for the cost of Part A and Part B services, as well as rebates, which must be used to reduce cost sharing, pay for extra benefits, or buy down the Part B and/or Part D premium (Figure 4). This growth is partly due to increased enrollment in Medicare Advantage plans, which rose from 33% to 54% of all eligible beneficiaries over this same period. At the same time, Medicare pays an estimated 14% more per enrollee in Medicare Advantage than it would if the same beneficiary were covered by traditional Medicare, resulting in $76 billion in additional Medicare spending in 2026. Those higher payments largely reflect the impact of higher coding intensity and favorable selection into Medicare Advantage. Growth in Medicare Advantage spending is projected to continue into the next decade, with payments to Medicare Advantage plans under for Part A and B benefits projected to increase to $1.3 trillion in 2035, or 59% of total Part A and Part B spending.

Payments to Medicare Advantage Plans Under Part A and B Nearly Tripled Between 2016 and 2025 (Line chart)

The Medicare Part A Trust Fund is Projected to be Depleted in 2033, Seven Years from Now

The depletion of the reserves in the Medicare Hospital Insurance (Part A) trust fund, which pays for inpatient hospital, skilled nursing facility, home health, and other Part A services, is projected to occur in the second quarter of 2033, based on the latest projections from the Medicare Trustees (Figure 5). This is one quarter earlier than the projection in last year’s report. According to the Medicare Trustees, the earlier depletion date is primarily the result of updated estimates of Social Security tax revenue (one source of Part A funding) that are lower than previously projected due to changes in the 2025 budget reconciliation bill (H.R. 1). If the reserves in the Part A trust fund are fully depleted, Medicare would not have sufficient funds to cover Part A benefit spending for the full year without additional revenues or reductions in spending on benefits or payments to providers.

Figure 5

Projected Increases in Medicare Spending Will Lead to Higher Medicare Premiums and Cost-Sharing Requirements

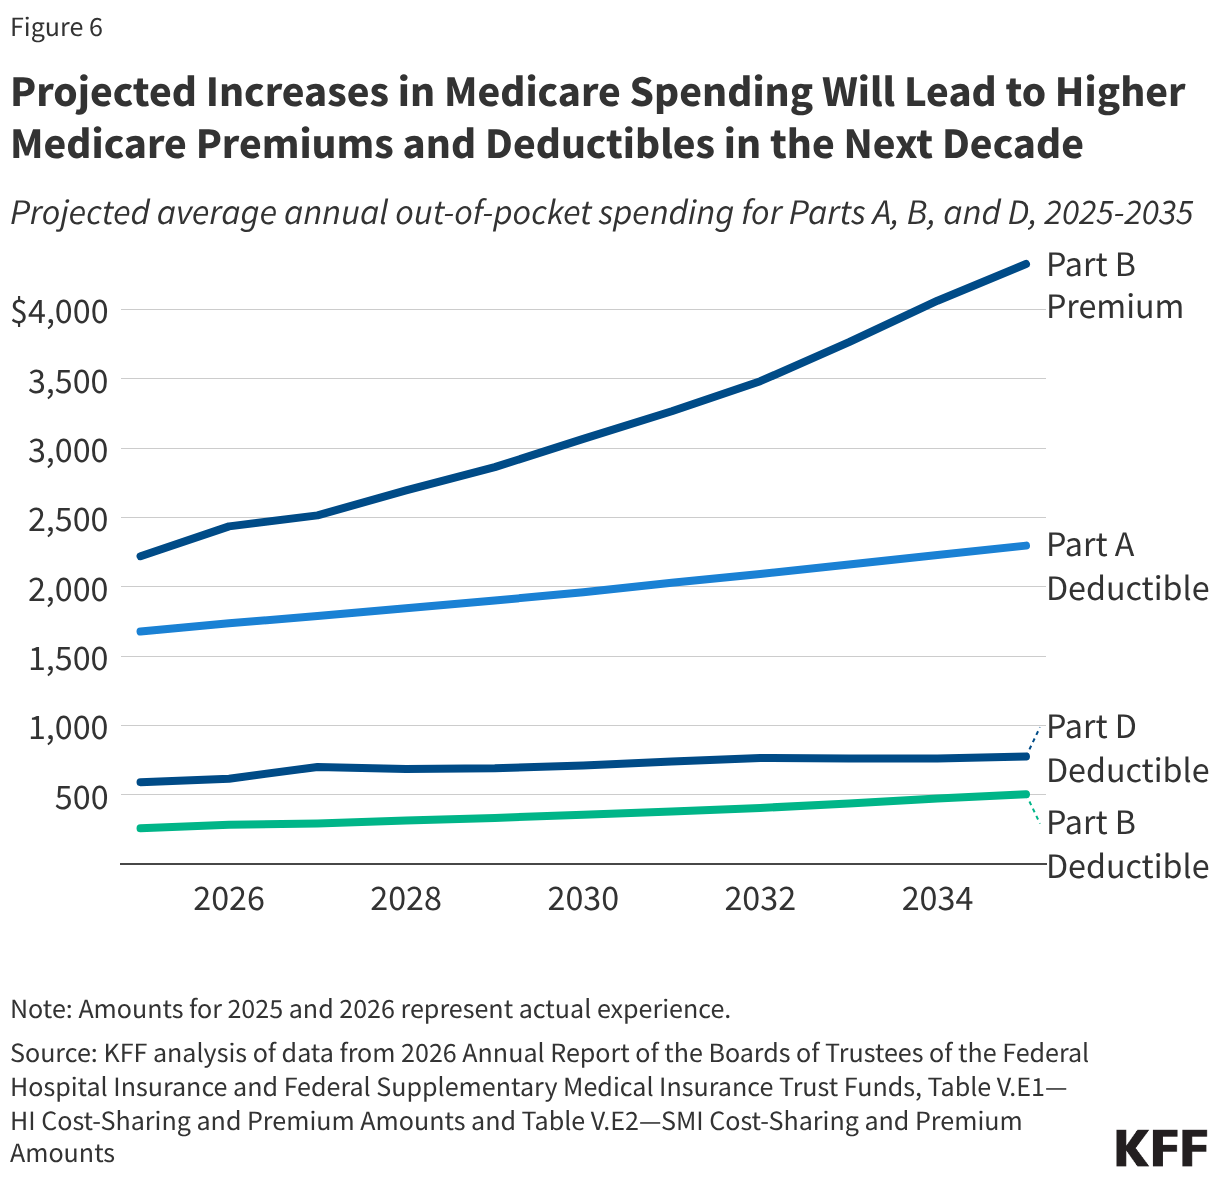
Medicare’s premium and cost-sharing requirements are determined annually based on expected growth in Medicare benefit costs for the coming year (though the exact approach to determining these amounts is different in each part). For 2027, the Trustees project that the monthly Part B premium will increase from $203 to $210 (3.3%), after increasing from $185 to $203 between 2025 and 2026 (9.7%). Likewise, the Part A hospital deductible is projected to increase from $1,736 to $1,788, and the Part D deductible from $283 to $292 in 2027. Further increases are estimated for the duration of the 10-year projection period in the 2026 Trustees report (Figure 6). These amounts may not reflect the costs that all beneficiaries face, particularly enrollees in Medicare Advantage plans, where cost sharing is generally different from the standard cost-sharing requirements for traditional Medicare beneficiaries. In 2024, seven million Medicare beneficiaries spent more than 10% of their income on the Part B premium alone. Increases in Medicare premiums and other out-of-pocket costs may represent a growing burden for many beneficiaries if income growth does not keep pace.

Projected Increases in Medicare Spending Will Lead to Higher Medicare Premiums and Deductibles in the Next Decade (Line chart)

U.S. Global Health Legislation Tracker

Published: Jun 23, 2026

This tracker provides a listing of global health-related legislation being considered by the 119th Congress (Jan. 3, 2025 – Jan. 3, 2027). Currently, there are more than 50 pieces of legislation related to global health. They address topics ranging from global health security to reproductive health to the World Health Organization (WHO). Sometimes a bill may address broader topics, but this tracker focuses on the global health aspects of the legislation.

The tracker includes the bill title, sponsor(s), current status, and topic, as well as a short description of its global health-related provisions. The tracker includes bills only; resolutions are not included. Legislation is listed in alphabetical order by short title. In certain cases, identical bills have been introduced in both chambers of Congress (often referred to as companion bills). For example, the Global Health, Empowerment and Rights Act and the WHO is Accountable Act were each introduced in both chambers. Such companion bills are listed separately in the tracker.

The tracker will be updated periodically.

Global Health Legislation During the 119th Congress
(as of June 17, 2026) (Table)

The Medical Frailty Exemption from Medicaid Work Requirements: Key Takeaways from the CMS Interim Final Rule

Published: Jun 23, 2026

On June 1, 2026, the Centers for Medicare and Medicaid Services (CMS) issued a long-anticipated interim final rule that will guide state implementation of Medicaid work requirements. The 2025 reconciliation law requires 44 states to condition Medicaid eligibility for adults in the Affordable Care Act (ACA) Medicaid expansion group and enrollees in certain waiver programs, including in non-expansion states (Georgia, Tennessee, and Wisconsin), on meeting work requirements starting January 1, 2027, or sooner at state option. The law specifies mandatory exemptions, including individuals who are “medically frail.” Given the abbreviated implementation timeline, states had tentatively moved forward with key decisions over how to implement the medical frailty exemption even as they waited for formal guidance from CMS.

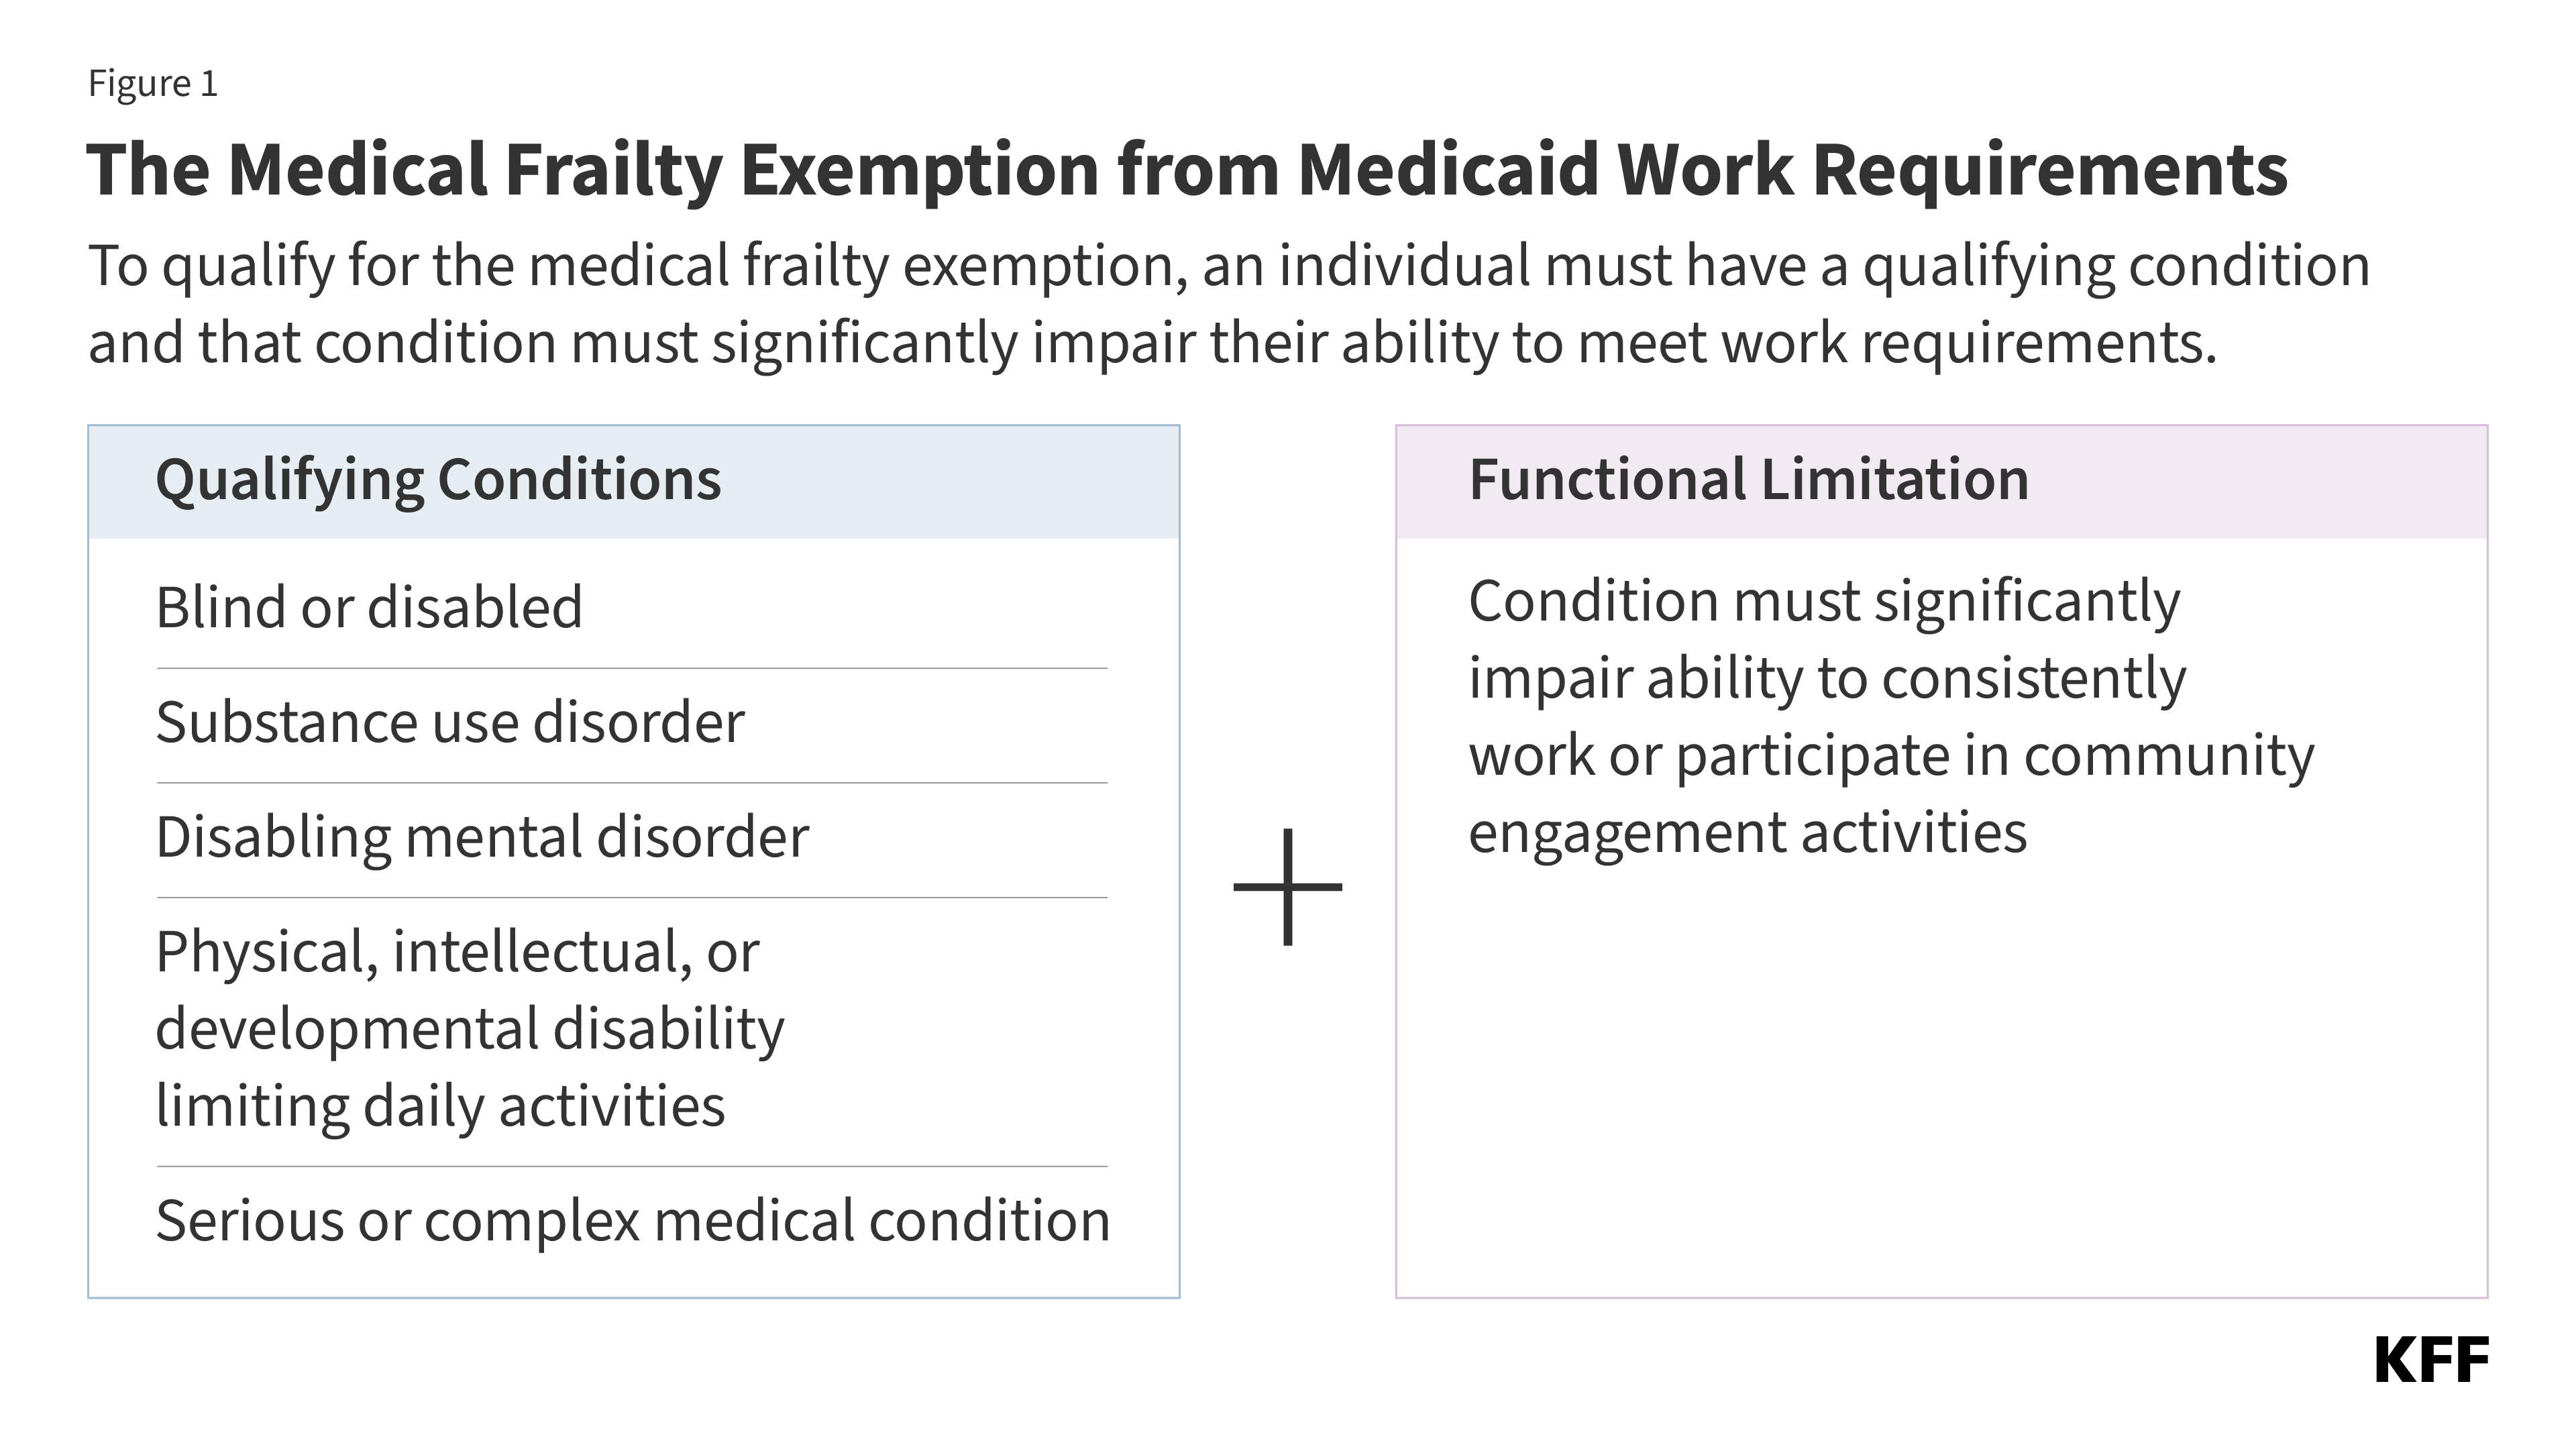
Significantly, the rule adopts a restrictive definition of medical frailty that differs from states’ early expectations and ties medical frailty to an individual’s ability to meet the community engagement requirements, including work or volunteer activities. The 2025 law specifies the medically frail exemption includes five categories of individuals who: are blind or disabled; have a physical, intellectual, or developmental disability that limits their ability to perform one or more activities of daily living (ADL); have a substance use disorder; have a “disabling” mental disorder; or have a “serious or complex” medical condition. The new rule requires states to consider not just whether the individual falls into one of the five categories described in the statute, but also whether the individual’s condition impairs their ability to engage in community engagement activities (including but not limited to work). States will likely need to pivot from earlier implementation plans and approaches to accommodate the new guidance.

States were already facing challenges in preparing to implement complex new requirements by January 1, 2027 and the provisions in the rule will amplify operational challenges, with added risks for states due to the potential for audits and financial penalties. The rule also may increase barriers for individuals to obtaining and maintaining coverage, leading to more people falling through the cracks and becoming uninsured. In addition, more complicated definitions of medical frailty may be difficult for states to explain as they conduct outreach with enrollees and potential applicants. This brief describes the new guidance and potential challenges states will face in operationalizing this exemption.

How Does the Interim Final Rule Define Medical Frailty?

For all categories of medical frailty, states are expected to develop a list of diagnosis and other codes to identify people who could potentially qualify for the exemption. States will be required to create lists of conditions that could potentially qualify someone as medically frail (generally in the form of health care code sets), which they must revise on a regular basis to reflect implementation experiences. CMS notes that the lists states use will be auditable, and if states are found to have determined an individual to be medically frail with little to no support for the conclusion that their physical, mental, or other behavioral health condition significantly impairs their ability to comply with the community engagement requirement, states would not be in compliance with the regulation and could be subject to financial penalties.

The rule relies heavily on existing definitions for the five medically frail categories and generally provides little additional clarification to help states develop the list of conditions for each category. In the rule, CMS said it did not believe it would be appropriate to include an exhaustive list of conditions in regulation, although they did provide examples of conditions across the various categories that could reasonably be expected to cause an individual to be medically frail. The rule acknowledges multiple existing definitions for several categories and ultimately defers to states the exact process of capturing individuals in these groups, explaining it “would be incredibly difficult to set one standard.” Notable details in the new rule include:

  • In the case of individuals with an SUD, the rule clarifies that the medical frailty category applies regardless of whether they are in an active treatment program but does not include individuals who have been in active recovery for 5 or more years.
  • For those with a serious or complex medical condition, the rule provides a new definition that requires a severe level of acuity for a condition to be considered serious or complex, which stands in contrast to other conceptions of “serious or complex” medical conditions that include individuals for whom maintaining access to health coverage is necessary to protect against serious health consequences if treatment is interrupted.

For all five categories, the rule makes clear that states must consider both if an individual’s condition meets the medical frailty definition and also if it significantly impairs their ability to work or engage in qualifying activities (Figure 1).

How Does the CMS Guidance Direct States to Verify Medical Frailty?

States are required to use claims and encounter data from the preceding 12 months to verify medical frailty status before requesting information from the individual; however, it will be difficult to use claims data alone to verify an individual’s ability to work. To ease the burden on individuals, the law directs states to use available information “where possible” to verify compliance with Medicaid work activities or exemption status, without requiring additional documentation from individuals. States are required to use claims or encounter data from the preceding 12 months as a data source. States are told they cannot consider information older than 12 months as this information “may not reflect the individual’s current condition.” The rule also encourages states to incorporate concise, plain language screening questions for use at application and renewal to identify individuals who may be medically frail. The rule is explicit that diagnosis alone cannot be used to verify medical frailty (because states must also consider whether an individual is sufficiently impaired from being able to work), limiting the ability of states to verify medical frailty on an ex parte (i.e., automatic) basis.

The rule does not provide details on criteria states should use for measuring severity of conditions or ability to meet new requirements. The rule only provides high-level examples of processes states may adopt to verify that an individual’s condition impairs their ability to work, such as algorithms that use administrative claims data to assign acuity scores, or using lists of qualifying diagnosis codes combined with utilization and other data. States may need to use combinations of data such as utilization data (e.g., hospitalizations), prescription drug data, and durable medical equipment (DME) prescription data. These approaches require states to implement even more complicated systems changes within the next six months that they were not anticipating based on earlier informal guidance. In addition, while these examples suggest states may be able to use acuity as a proxy for an individual’s ability to work, the rule is not clear on how states are expected to make these determinations. With the potential for audit, states may struggle to operationalize the medical frailty exemption in a way that protects them from financial penalty and minimizes administrative burden, without denying coverage to individuals who should qualify for the exemption.

Data limitations make it likely that medical frailty determinations will not be automated for many individuals. Examples of limitations include lack of data on file for new applicants and recent enrollees, or providers not consistently coding conditions or not using codes identified by the state. Certain individuals, such as those with functional limitations or behavioral health conditions, may also be more difficult to identify using claims data. States are also not provided with clear guidance on how to assess whether an individual is able to work or engage in community engagement activities, including what type of work activities states must consider. The more individualized the required assessment is, the more difficult it will be for states to auto-exempt individuals using data.

While states may need to rely on confirmation from treating providers to verify medical frailty conditions and ability to participate in community engagement activities, the rule offers little information on what information states need to collect from providers. States choosing to accept provider documentation are told that lists of who they choose to be allowable practitioner types must be shared with CMS if requested as part of oversight and data monitoring activities. Relying on provider confirmation could increase administrative burden (on the clinical workforce, individuals, and states), particularly for providers that treat large shares of Medicaid patients. Relying on providers or eligibility workers to determine whether an individual is able to work will likely require a subjective decision and could raise ethical concerns among providers. New Hampshire had previously implemented work requirements with a requirement that individuals needed to be deemed unable to work by providers to qualify for an exemption; enrollees with physical and behavioral health problems struggled when applying for exemptions, often because primary care providers resisted signing forms declaring that their patients were unable to work. Research also shows that physician attitudes to assisting patients who request exemptions from work requirements can vary substantially. In addition, because providers receive Medicaid payments and, therefore, have an interest in their patients maintaining health coverage, requesting information from them to confirm a medical frailty exemption could raise conflict of interest issues.

While states are permitted to use self-attestation to verify medical frailty, the rule limits reliance on self-attestation starting in January 2028. Given the limitations of existing data sources and the difficulty of identifying whether an individual is medically frail, accepting self-attestation of medical status or ability to work could relieve the administrative burden for states as well as applicants and enrollees. Acknowledging data limitations states face particularly for new applicants, the rule allows states to accept self-attestation throughout 2027 in cases where there is no reliable information available to the state. However, starting January 1, 2028, states may only accept self-attestation of medical frailty status one time during an individual’s enrollment period. States would then be expected to verify individuals using available data or require documentation or other information from individuals for future renewals.

The rule requires states to verify medically frail exemption status at least every 12 months. States must reverify medical frailty even for people whose health condition or disability status is unlikely to change every 12 months; however, the rule gives states the option to reverify medical frailty more frequently (such as at each 6-month renewal period). For states that elect to verify compliance between regular renewals (e.g., quarterly), the rule specifies that individuals identified as specified excluded individuals during their most recent verification, including those who meet medical frailty exemptions, are not subject to more frequent verifications.

The Business of Health with Chip Kahn

Is AI (Still) Biased? 

June 23, 2026

Video

Audio

About this Episode


Episode 9, AI Series: In this episode, Dr. Ziad Obermeyer joins Chip to talk about AI bias in patient management, including how far the health care industry has come since his groundbreaking research that revealed alarming biases in a widely used algorithm that underestimated the health needs of Black patients. The discussion emphasizes that while AI can analyze data with remarkable precision, it is the context surrounding that data that ultimately determines its efficacy, usefulness, and fairness. Dr. Obermeyer is an emergency department physician, researcher, co-founder of Nightingale Open Science and Dandelion, and associate professor at the UC Berkeley School of Public Health and the College of Computing, Data Science, and Society. 

The Host


Headshot photo of Chip Kahn wearing a navy blue suit with a red tie, red pendant on lapel, and glasses.

Sr. Visiting Fellow

Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.

Guest


Blue Cross of California Distinguished Associate Professor of Health Policy and Management, UC Berkeley School of Public Health

Dr. Ziad Obermeyer is Associate Professor and Blue Cross of California Distinguished Professor in UC Berkeley’s School of Public Health and College of Computing, Data Science, and Society. His work, grounded in clinical practice, uses AI and data to improve clinical decisions, accelerate medical discovery, and bring computational innovations into patient care. His research on algorithmic bias has influenced hospital AI practices worldwide and informed public accountability efforts. He co-founded Nightingale Open Science and Dandelion and is a Chan–Zuckerberg Biohub Investigator and a Research Associate at the National Bureau of Economic Research. A Harvard Medical School faculty member and McKinsey consultant, he was named to TIME Magazine’s 100 most influential people in AI.  


SERIES

This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.

The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.

The Role of Immigrants in the U.S. Health Care Workforce

Published: Jun 18, 2026

Introduction

The Trump administration has made policy changes to restrict immigration into the U.S., including efforts to end Temporary Protected Status (TPS) designations for many countries, pauses and restrictions on the issuance of new visas, and significantly increased immigration enforcement. These actions could have negative implications for the U.S. workforce, which includes significant shares of immigrant workers, particularly in certain industries including health care. Immigrant workers include naturalized citizens as well as noncitizens, including lawfully present and undocumented immigrants.

This issue brief provides data on immigrants’ role in the U.S. workforce, including in health care and other key industries, based on KFF analysis of Current Population Survey (CPS) basic monthly data and American Community Survey (ACS) one-year data for U.S. workers 18 years and older by citizenship status. Key takeaways from this analysis include:

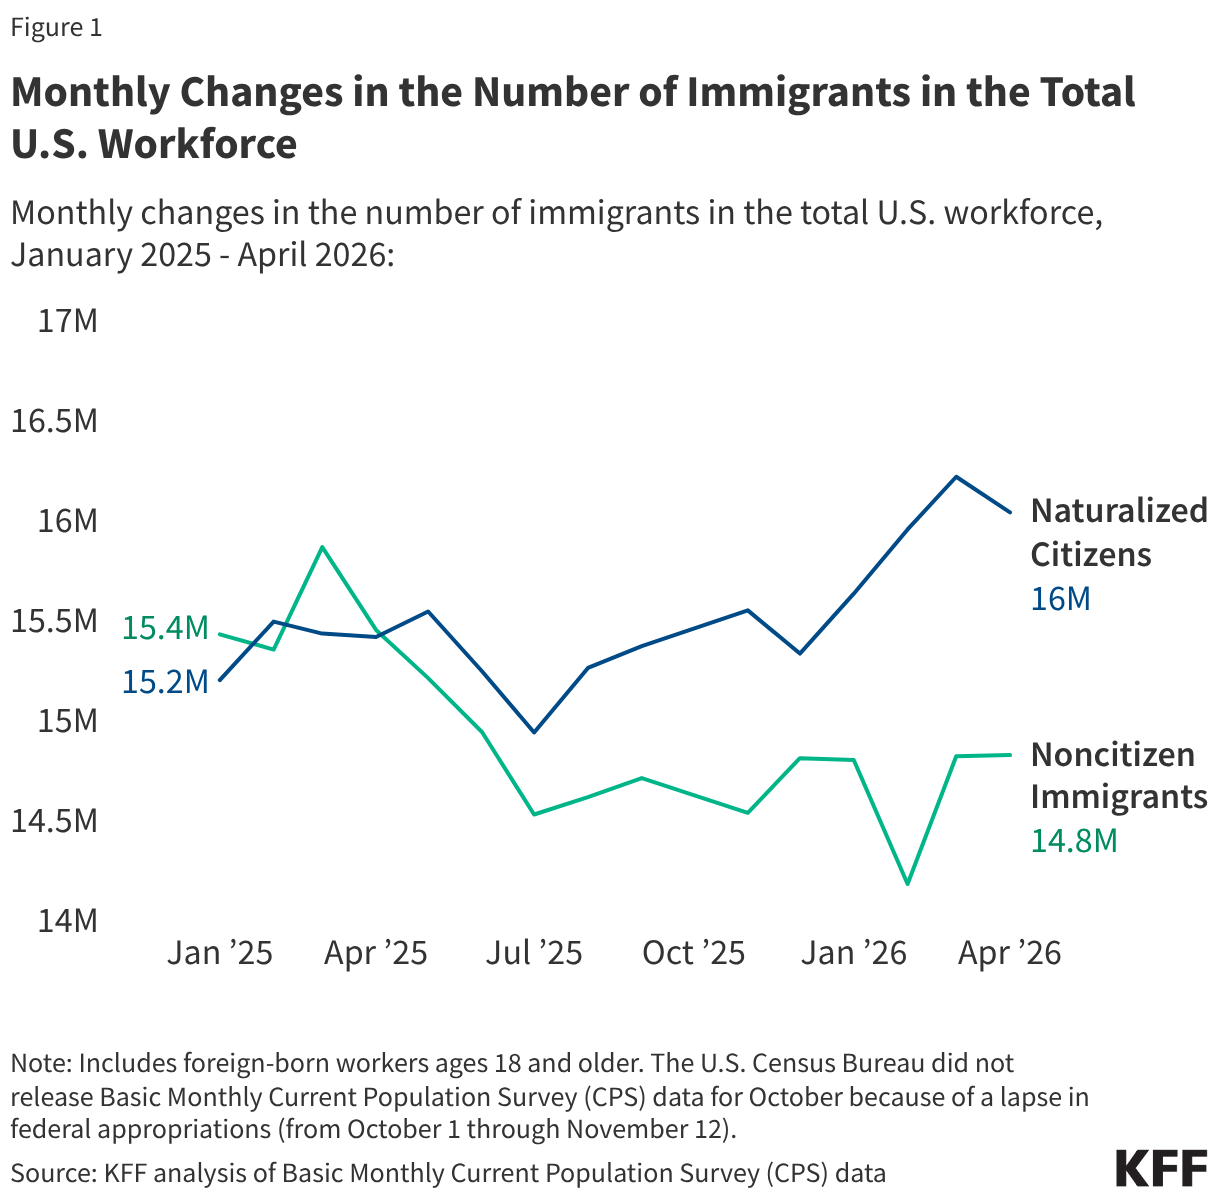
While the total number of immigrant workers in the U.S. held largely steady between January 2025 and April 2026, the number of noncitizen immigrant workers declined by about 600,000, or 4%, from 15.4 million to 14.8 million. This was offset by an increase in the number of naturalized citizen workers of over 800,000, or about 6%, from about 15.2 to 16.0 million. The number of U.S.-born workers increased by about 1% between January 2025 and April 2026 (125.6 to 126.7 million). Within the health care industry, there was an overall increase of 1% or about 130,000 workers from 19.4 to 19.6 million, which reflected increases among U.S-born (16.0 to 16.1 million) and noncitizen immigrant workers (961,000 to 1.2 million) that offset a decline among naturalized citizen workers (2.5 million to 2.3 million).

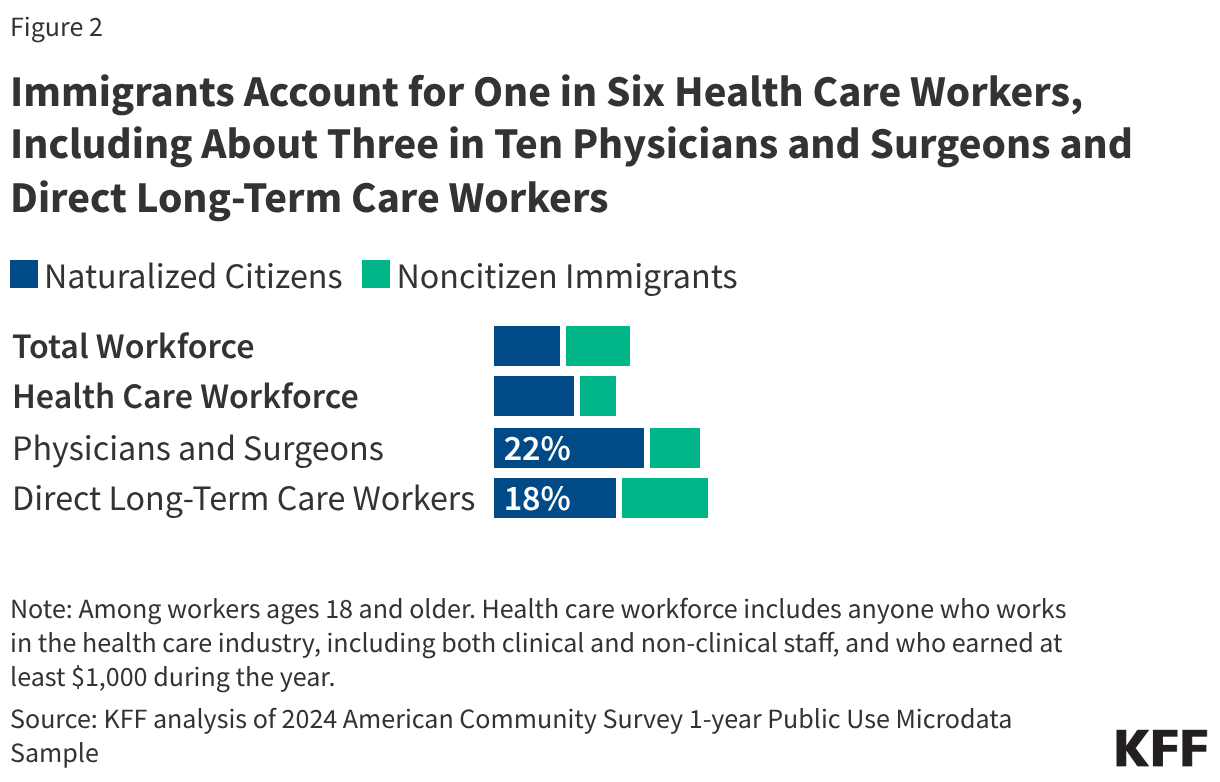
Immigrants accounted for about one in five (19%) or close to 31 million of the total U.S. workforce as of 2024. Within health care, immigrants accounted for 17% of the workforce, including 28% of physicians and surgeons and 30% of direct care workers in long-term settings. In hospitals, immigrants accounted for similar shares of clinical staff and non-clinical staff and played a particularly large role as physicians and surgeons (30%). Top countries of origin for immigrant health care industry workers include Philippines (12%), Mexico (11%) and India (7%). In hospitals, immigrants also play an outsized role in certain non-clinical occupations, including building cleaning and maintenance workers (29%). Immigrants, particularly noncitizen immigrants, also accounted for disproportionate shares of agriculture (33%); construction (26%); and food services, maintenance, and personal care service workers (23%).

Continued reductions in the number of immigrants could impact the U.S. economy and key industries, especially as the 65 and older population in the U.S. grows and there are fewer replacement workers available. Reduced immigrant participation in the health care workforce, including the long-term care workforce, could exacerbate existing worker shortages and negatively impact the health and well-being of Americans.

While the total number of immigrant workers in the U.S. held largely steady between January 2025 and April 2026, the number of noncitizen immigrant workers declined by about 600,000 or 4% from 15.4 million to 14.8 million. This was offset by an increase in the number of naturalized citizen workers of over 800,000, or about 6%, from about 15.2 to 16.0 million. The number of U.S.-born workers increased by about 1% between January 2025 and April 2026 (125.6 to 126.7 million). Within the health care industry, there was an overall increase of 1% or about 130,000 workers from 19.4 to 19.6 million, which reflected increases among U.S-born (16.0 to 16.1 million) and noncitizen immigrant workers (961,000 to 1.2 million) that offset a decline among naturalized citizen workers (2.5 million to 2.3 million).

Monthly Changes in the Number of Immigrants in the Total U.S. Workforce (Line chart)

Immigrants’ Role in the U.S. Health Care Workforce

Changes in the immigrant workforce may have important implications given the role that immigrants play, particularly in certain industries including health care.

Immigrants account for about one in five workers in the U.S. As of 2024, immigrants accounted for about 19%, or close to 31 million, of the total U.S. workforce over age 18 based on KFF analysis of ACS data. Naturalized citizens accounted for roughly 10% of workers and noncitizen immigrants accounted for another 9% of total workers.

Within health care, immigrants make up about one in six workers overall and account for even larger shares of physicians and surgeons and direct care workers in long-term settings. Immigrants accounted for 17%, or about 3.3 million, of the health care workforce overall and about three in ten physicians and surgeons (28%) and direct care workers in long-term care settings (30%) (Figure 2). Among physicians and surgeons, 22% were naturalized citizens and 7% were noncitizen immigrants. Among direct long-term care workers, 18% were naturalized citizens and 12% were noncitizen immigrants.

Immigrants Account for One in Six Health Care Workers, Including About Three in Ten Physicians and Surgeons and Direct Long-Term Care Workers (Stacked Bars)

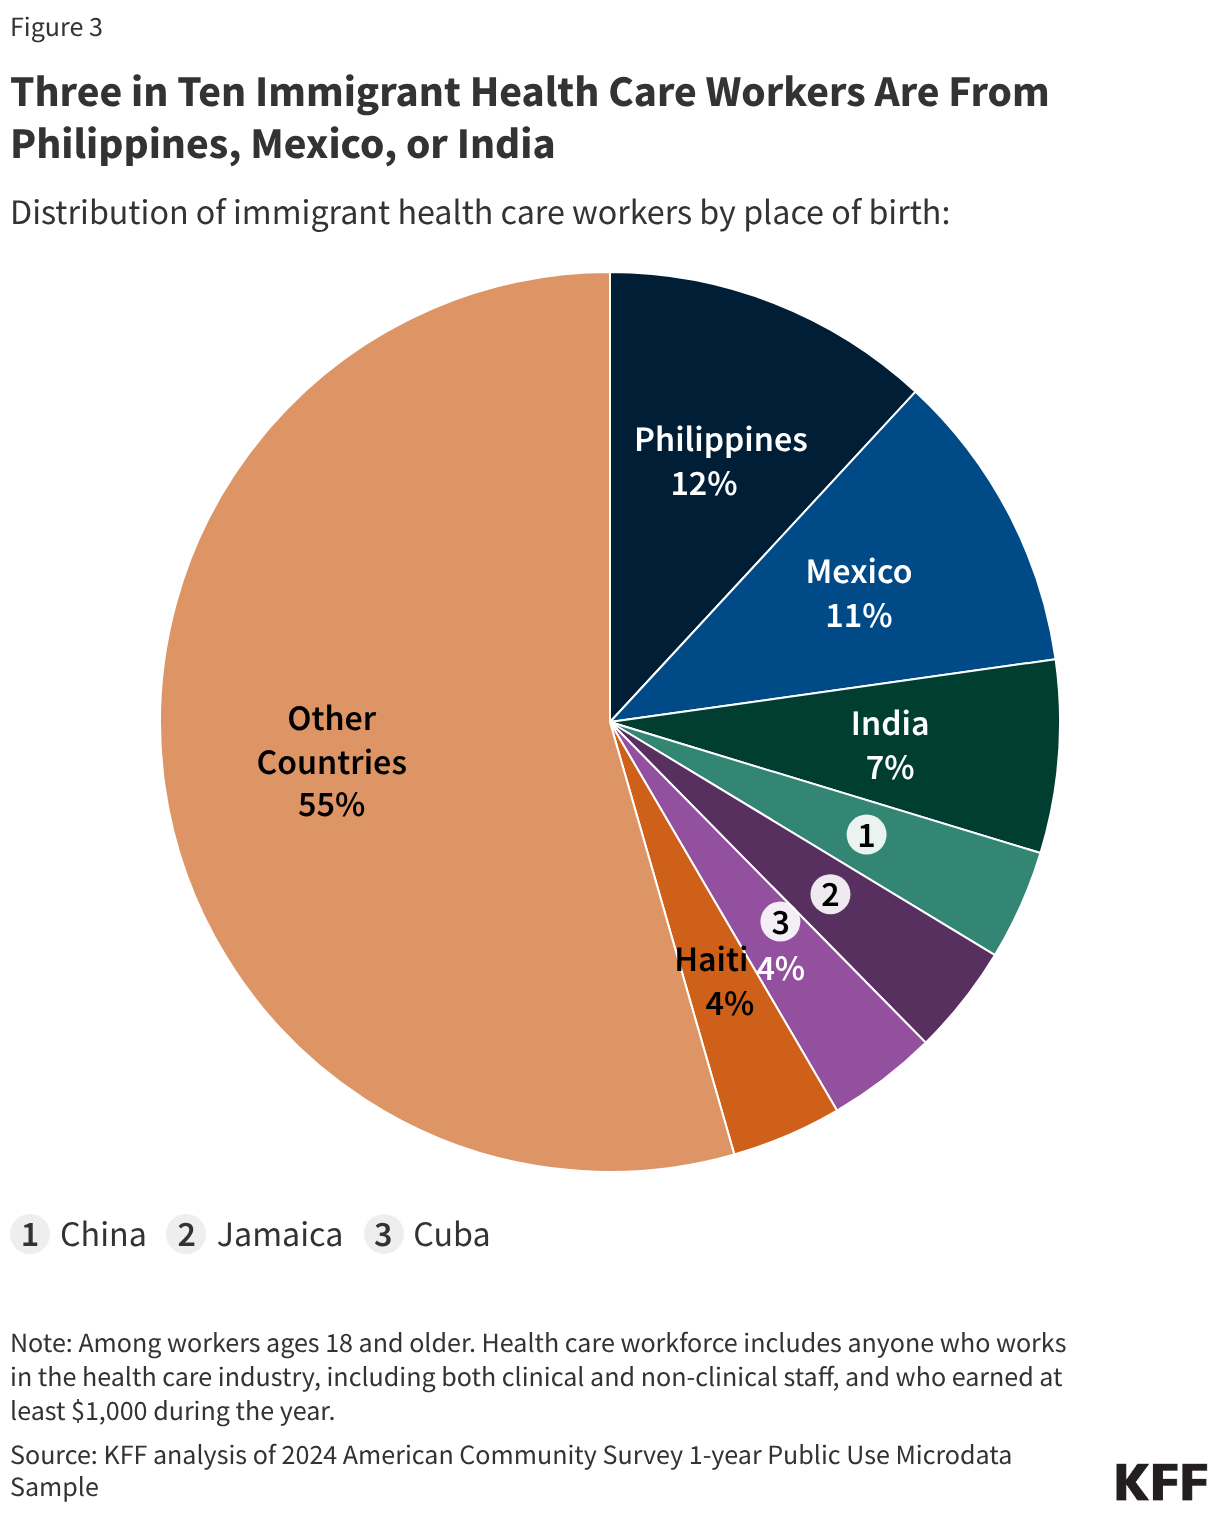
Three in ten immigrant health care workers are from Philippines (12%), Mexico (11%) or India (7%) (Figure 3).  China, Jamaica, Cuba, and Haiti contribute another 4% each of immigrant health care workers. Among immigrant physicians and surgeons, one in five (21%) are from India, 6% from China, 5% each from Canada and Pakistan, and 4% are from Philippines. Among immigrant direct long-term care workers, one in seven (14%) are from Mexico, 7% each are from Dominican Republic and Philippines, and 6% each are from Jamaica, China, and Haiti.

Three in Ten Immigrant Health Care Workers Are From Philippines, Mexico, or India (Pie Chart)

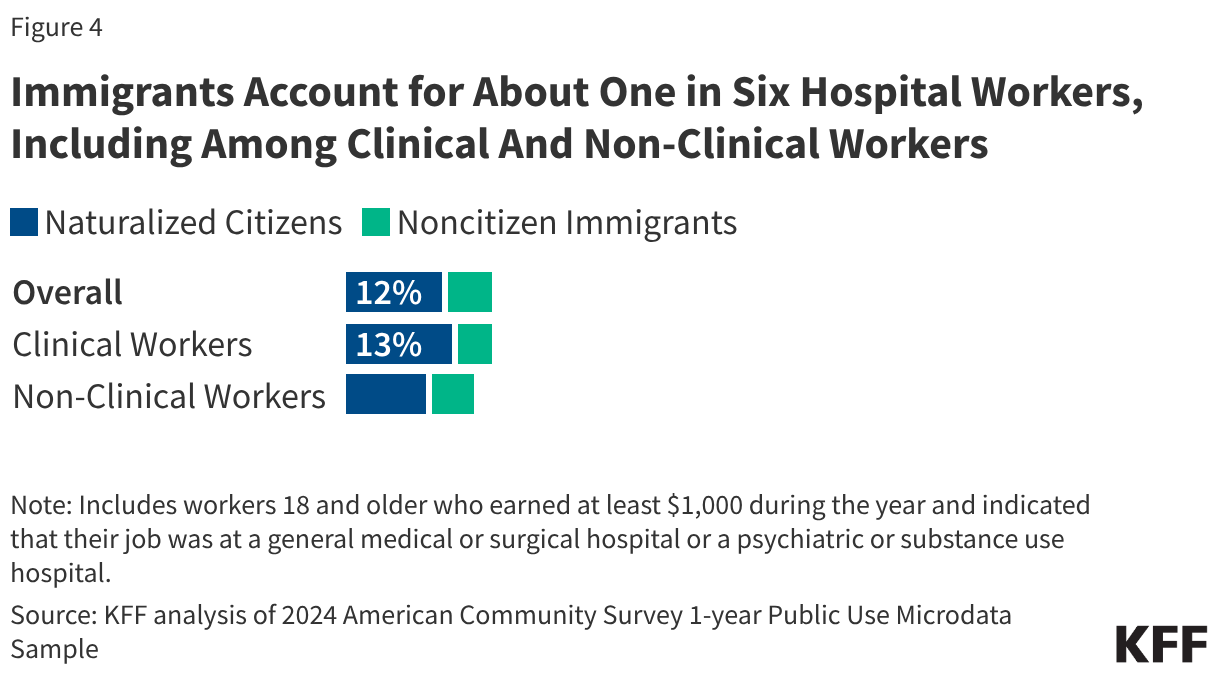
In hospitals, immigrants accounted for one in six (17%), or about 1.4 million, workers as of 2024. This includes 12% of hospital workers who are naturalized citizens and 5% who are noncitizen immigrants (Figure 4). Immigrants made up similar shares of clinical (17%) and non-clinical (15%) workers in U.S. hospitals. Clinical workers include physicians, surgeons, nurses, etc., and non-clinical workers include office workers, food service workers, cleaning and maintenance workers, and other non-clinical workers. Among immigrant hospital workers, 16% are from Philippines, 9% are from Mexico, 8% are from India, and 4% each are from China and Jamaica.

Immigrants Account for About One in Six Hospital Workers, Including Among Clinical And Non-Clinical Workers (Stacked Bars)

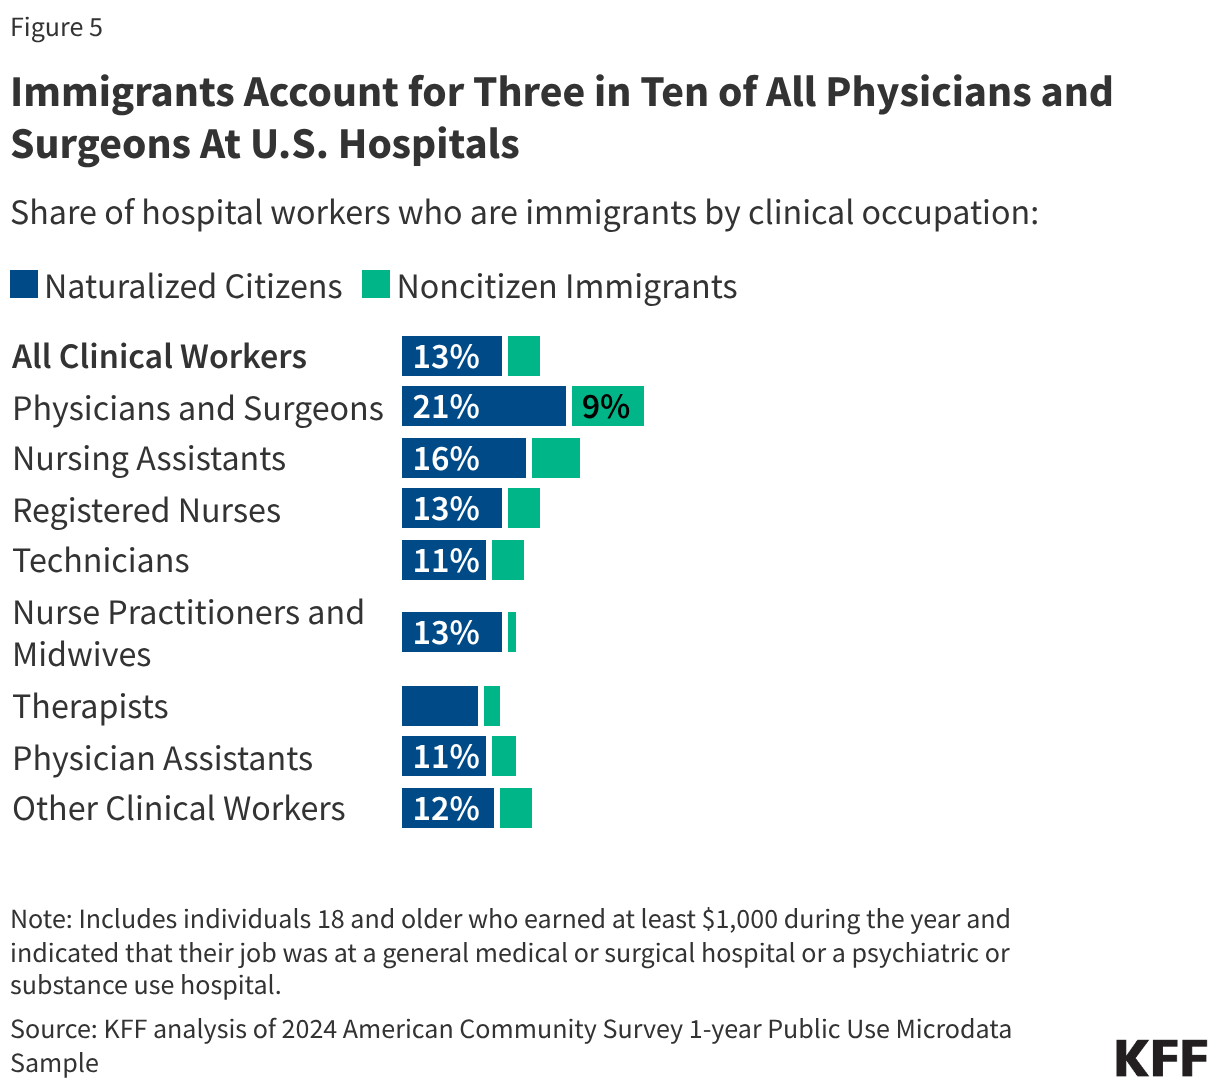
Within hospitals, immigrants made up three in ten (30%) physicians (Figure 5). This includes over one in five (21%) who are naturalized citizens and another 9% who are noncitizen immigrants. Immigrants also made up over one in five (22%) nursing assistants, about one in six registered nurses (17%), and about one in seven technicians (15%) and nurse practitioners and midwives (14%) at U.S. hospitals. Immigrants also play an outsized role in certain non-clinical occupations in hospitals, such as building cleaning and maintenance workers.

Immigrants Account for Three in Ten of All Physicians and Surgeons At U.S. Hospitals (Stacked Bars)

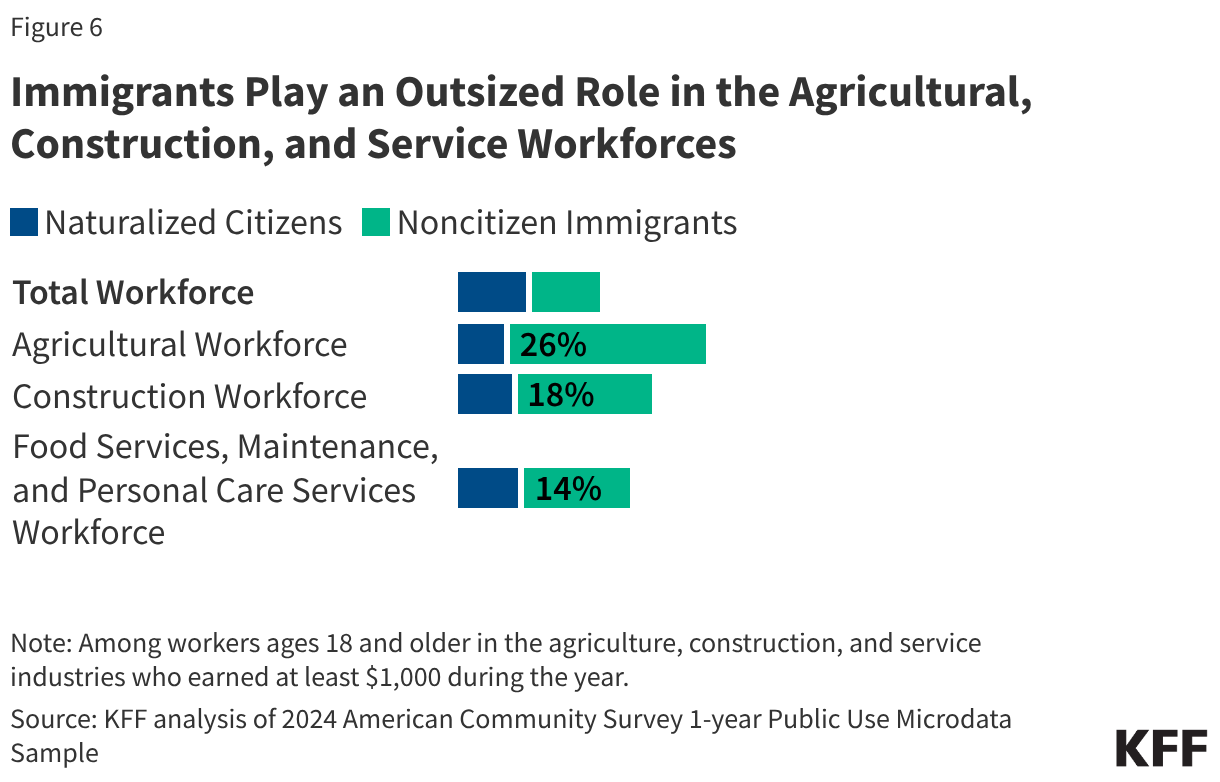
Immigrants, particularly noncitizen immigrants, also play an outsized role in other key industries including agriculture, construction, and service. As of 2024, immigrants made up one in three (33%) agricultural workers, of whom 26% were noncitizen immigrants and 7% were naturalized citizens; about a quarter of (26%) construction workers, of whom 18% were noncitizen immigrants and 8% were naturalized citizens; and about a quarter (23%) of food services, maintenance, and personal care service workers, of whom 14% were noncitizen immigrants and 9% were naturalized citizens (Figure 6).

Immigrants Play an Outsized Role in the Agricultural, Construction, and Service Workforces (Stacked Bars)

Methods

Data sources: This brief is based on KFF analysis of federal survey data, namely the Basic Monthly Current Population Survey (CPS) and the American Community Survey 1-year Public Use Microdata Sample. These surveys are nationally representative household surveys conducted by the U.S. Census Bureau. While Basic Monthly CPS data are available on a monthly basis, ACS PUMS data are available on a yearly basis. Basic Monthly CPS data have a significantly smaller sample size than yearly ACS and yearly CPS data. Due to the smaller sample size, results may be more sensitive to potential decreases in survey participation among immigrants due to immigration-related fears.

Identifying citizenship status: Naturalized citizens are those who indicate becoming a U.S. citizen by naturalization; and noncitizen immigrants are those who say that they are not a U.S. citizen. Noncitizen immigrants include lawfully present and undocumented immigrants.

Identifying workers across different industries: Health care, agriculture, construction, and service workers are identified as individuals 18 years of age or older who report working either full-time or part-time in one of the aforementioned industries and who earned at least $1,000 during the year. Industries are classified based on Census codes that correspond with the North American Industry Classification System (NAICS). Codes 0170 through 0290 correspond to the agriculture industry; 0770 corresponds to the construction industry; 7970 through 8290 correspond to the health care industry; and 8680 through 9070 correspond to the food services, maintenance, and personal care services industries.

Identifying hospital and direct long-term care workers: Hospital workers are individuals 18 years or older who report working either full-time or part-time and indicate that their job was at a general medical or surgical hospital or a psychiatric or substance use hospital and who earned at least $1,000 during the year. Direct long-term care workers are individuals 18 years or older who report working either full-time or part-time, earned at least $1,000 during the year, and whose occupation is home health aide, personal care aide, or nursing assistant and who indicate working in home health care, nursing care facilities, residential care facilities, or individual and family services.

Poll Finding

KFF Tracking Poll on Health Information and Trust: Use of Social Media and AI For Health Information and Advice

Published: Jun 17, 2026

Key Takeaways

  • Adults in the U.S. are turning to social media and AI to advise them on health issues. KFF’s latest Tracking Poll on Health Information and Trust finds three in ten adults (31%) using social media at least monthly for health information and advice. This is similar to the share (29%) who now say they use AI tools or chatbots for health information monthly, a number that has nearly doubled in the past two years – up from roughly one in six (17%). Still, majorities say they either “never” or only “occasionally” use AI tools (71%) or social media (69%) for health information.
  • Although some people turn to both social media and AI for health information, the two audiences are demographically distinct. While younger adults are more likely than older adults to use social media and AI for health information, the youngest cohort is much more likely to rely on social media while 30 to 49 year olds are more likely to turn to AI. Additionally, social media tends to attract lower-income adults, while AI use is more common among those with higher incomes or more advanced education. Hispanic adults stand out as notable adopters of both platforms for health information, unlike White adults, who are less likely to use either as a source of information.
  • Need for community and immediacy of information drives use of social media for health information and advice. Over a third of those who use social media for health information and advice report that wanting to learn from people with the same health condition or similar experiences is a “major reason” (36%) they turned to social media. A similar share (35%) say it is because they want immediate information or support. While fewer (17%) say that not having a regular health care provider or not being able to afford the cost is a “major reason” for turning to social media, that number rises to a third among adults without insurance and LGBT adults. Notably, similar shares say not being able to afford the cost of seeing a provider (19%) or not having a regular health care provider (18%) are both a “major reason” why they used AI tools for health information in KFF’s March 2026 Tracking Poll on Health Information and Trust as said the same for a reason why they used social media in this poll.
  • The majority of social media and AI users are confident in their ability to parse true or false information, which is perhaps why few take steps to validate the information either from a doctor or some other source. Less than four in ten adults who use social media for health information follow up with a doctor at least most of the time (36%), consult another online source like WebMD (35%), or check with health agency websites, like the CDC (21%).

Social Media and AI Use for Health Information

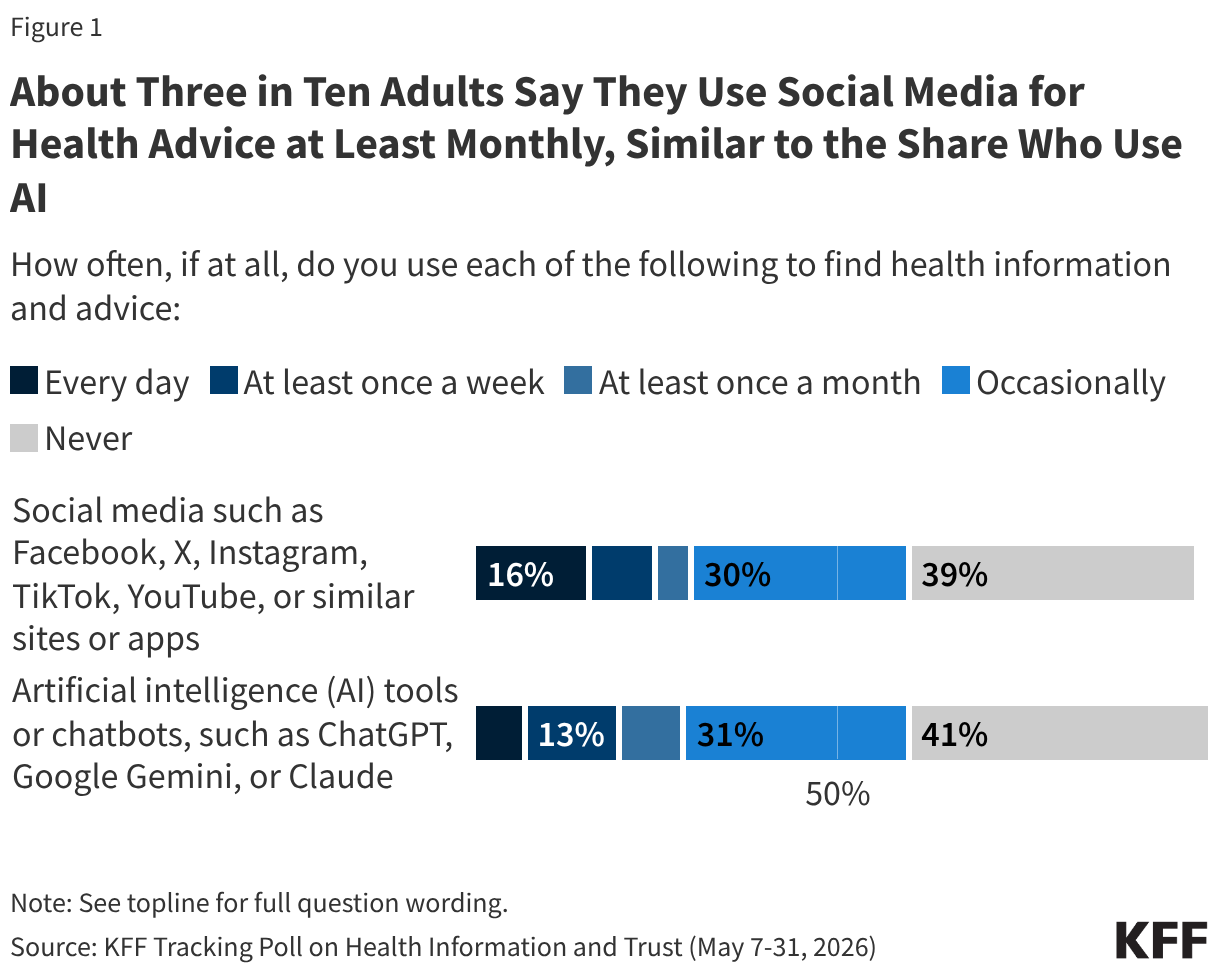
Three in ten adults report using social media for health information or advice at least once a month. This includes about one in six (16%) who say they use it “every day.” Similarly, three in ten (29%) adults now say they use artificial intelligence (AI) tools or chatbots like ChatGPT, Google Gemini, or Claude for health information and advice monthly, nearly doubling in the past two years, up from roughly one in six (17%) in June 2024. Though they provide health information in different ways, the growing use of these technologies suggests that adults are looking beyond traditional health care sources. Still, a majority of the public say they either “never” or only “occasionally” use AI tools (71%) or social media (69%) for this.

Stacked bar chart showing how often people report using social media or AI tools for health information and advice.

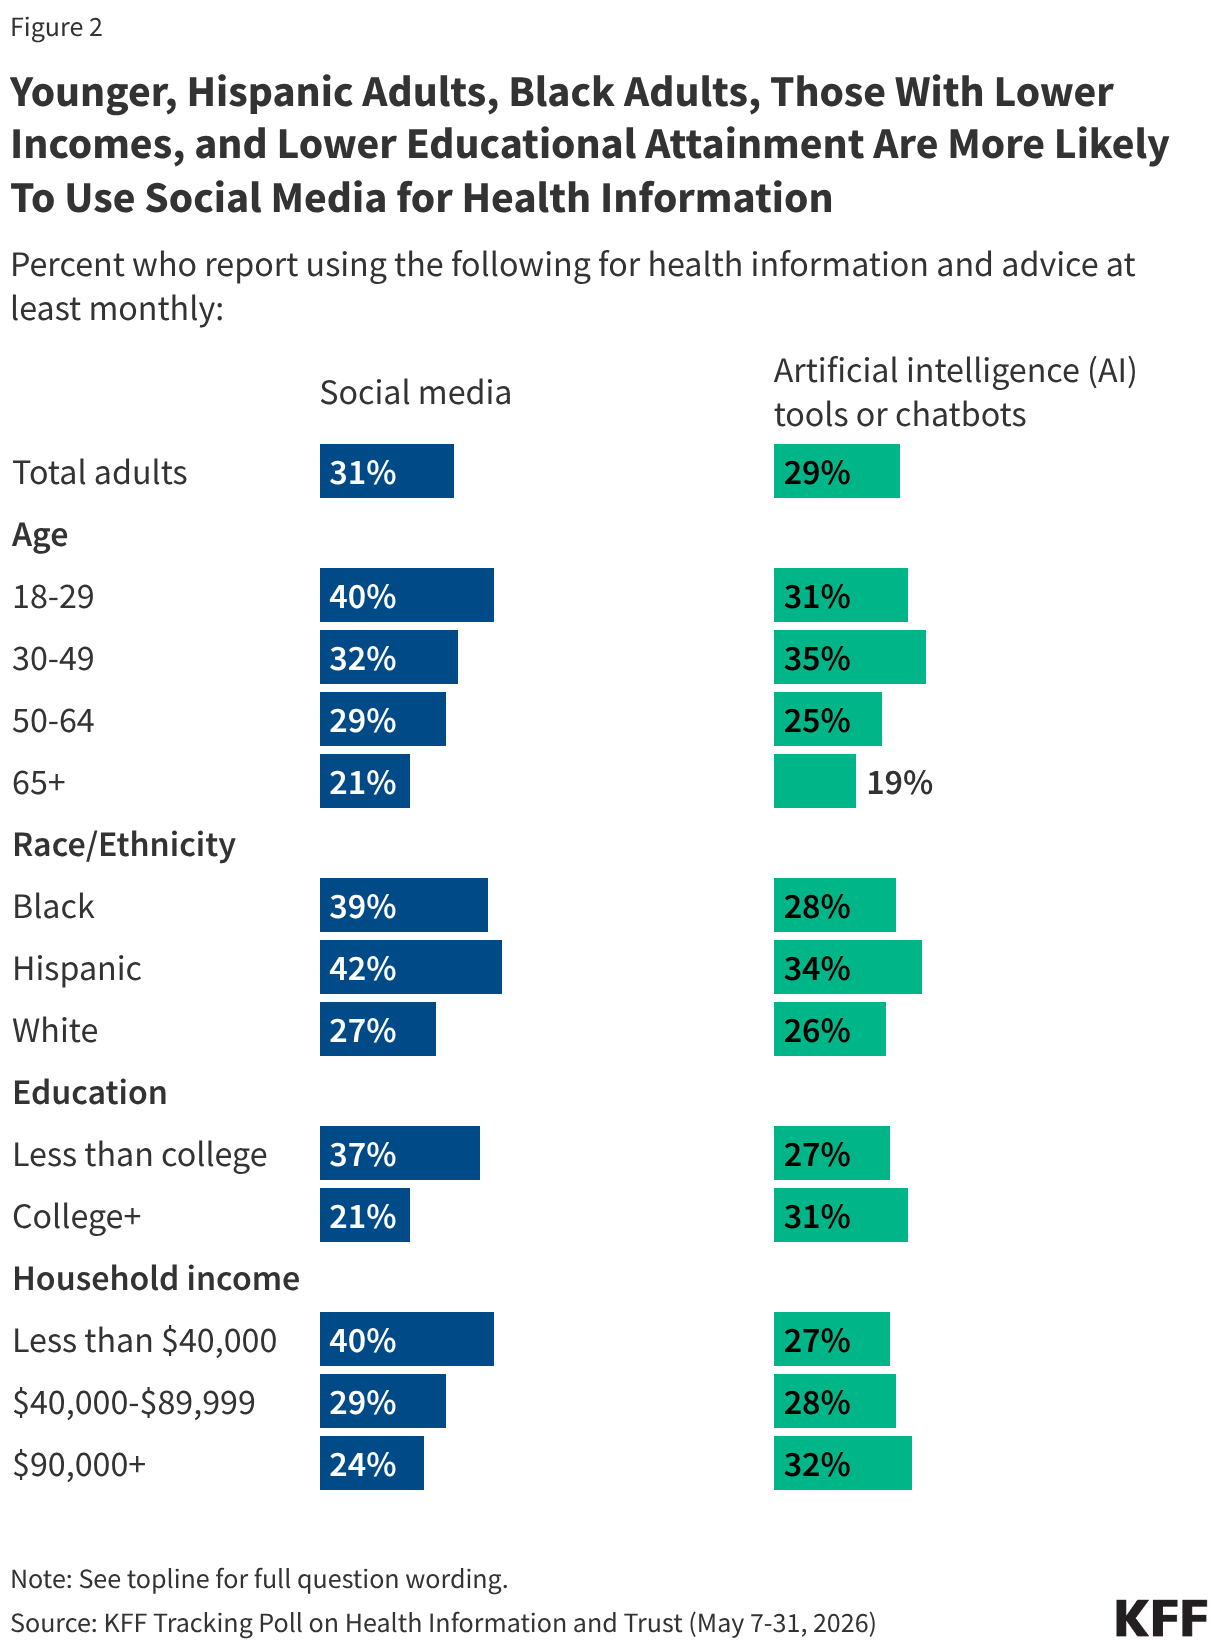
Younger adults (ages 18 to 29), Hispanic adults, Black adults, and those with lower incomes are among the most likely groups to use social media for health information. About four in ten Hispanic adults (42%), those with incomes of $40,000 or less a year (40%), adults under the age of 30 (40%), and Black adults (39%) say they use social media for health information at least monthly.

On the other hand, AI use for health information is common among the youngest cohort (ages 18 to 29) as well as those ages 30 to 49. While those with lower levels of education and income are more likely to go to social media for health information, there is less variation with reliance on AI with about three in ten across income and education groups reporting using it at least monthly. Notably, larger shares of Hispanic adults report using both social media and AI for health information, compared to White adults.

Split bar chart showing the percent of people who report using social media or AI tools for health information and advice at least monthly. Results by total adults, age, race/ethnicity, education, and household income.

Reasons for Using Social Media

People report using social media for health information for a variety of different reasons. Among those who use social media for health information and advice (60% of total adults), over a third (36%) say that wanting to learn from people who have the same health condition or share similar experiences is a “major reason” why. A similar share (35%) says a “major reason” was wanting immediate information or support. Fewer (17%) say that not having a regular health care provider or not being able to afford the cost of seeing a provider is a “major reason” why they turned to social media for health information, though about four in ten (42%) say that it is a reason.

Stacked bar chart showing the percent of people who selected wanting to learn from others, wanting immediate information, and not having a regular health care provider as a reason for using social media to find health information and advice.

The use of social media for health information and advice because of a lack of a regular health care provider or not being able to afford the cost is higher among groups that have historically had a harder time accessing health care. Among social media users, roughly three in ten uninsured adults (32%) say this was a “major reason” and another four in ten (37%) say it is a “minor reason” they turned to social media. Adults with lower incomes are more likely than those with higher incomes to report that not having a regular provider is a “major reason” for using social media for health information, with a quarter of those with an income of less than $40,000 a year saying so, compared to two in ten (19%) of those with an income of $40,000 to $89,999, and less than one in ten (6%) of those with a yearly income of $90,000 or more. LGBT adults are also more likely to say this is a reason they used social media, with three in ten LGBT adults reporting this was a “major reason” and a quarter (24%) saying it’s a “minor reason.” LGBT adults are also more likely to have lower incomes generally, possibly explaining some of the access issues they report, though they may lack a provider due to stigma and discrimination related issues.  

Additionally, larger shares of Hispanic adults (29%) and Black adults (23%) report that not having a regular provider is a “major reason” for seeking advice through social media than White adults (12%).

Stacked bar chart showing the percent of people who said not having a regular health care provider was a reason for using social media to find health information and advice.

Notably, similar shares said not being able to afford the cost of seeing a provider (19%) or not having a regular health care provider (18%) were both a “major reason” why they used AI tools for health information in KFF’s March 2026 Tracking Poll on Health Information and Trust as said the same for a reason why they used social mediain this poll (17%).

Stacked bar chart showing the percent of adults who said not having a regular health care provider, or being unable to afford or get an appointment with one, was a major reason, minor reason, or not a reason they used social media or AI tools for health information and advice.

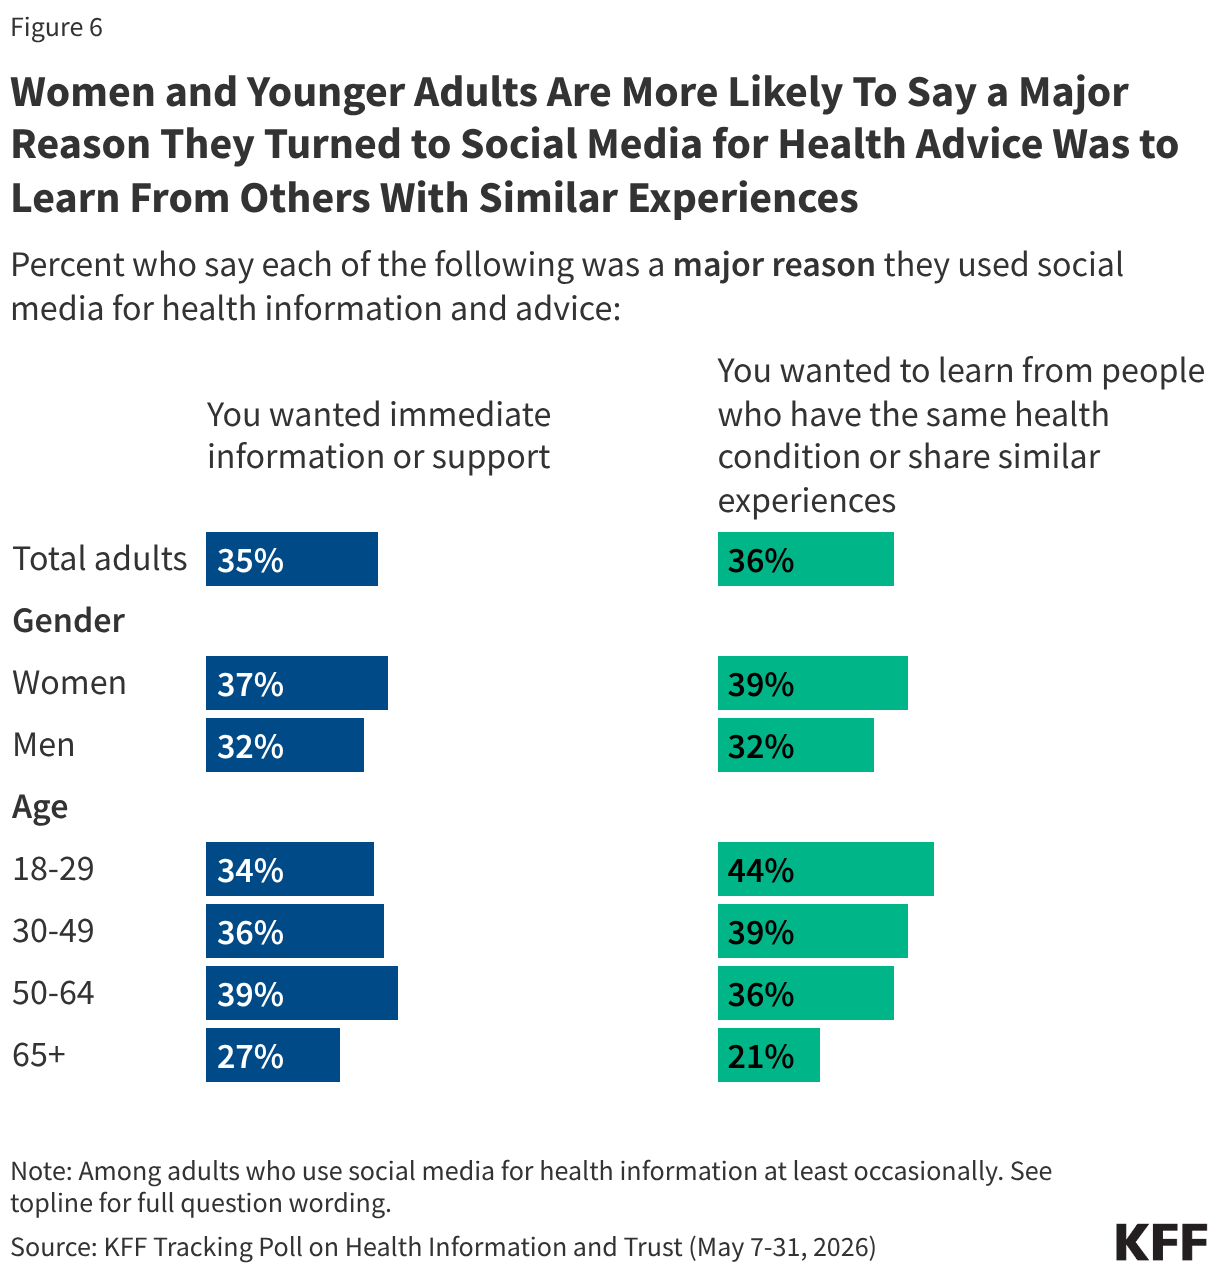
Women are more likely than men to say that they wanted to learn from people who have the same health condition or shared similar experiences (39% of women v. 32% of men). Young adults under the age of 30 are also among the most likely to say wanting to learn from people with the same condition or experiences is a “major reason” why they sought out health information on social media (44% of those ages 18 to 29 v. 21% of those ages 65 and older).

Split bar chart showing the percentage of adults who said wanting immediate information or support and wanting to learn from people with similar health conditions or experiences, was a major reason they used social media for health information and advice, broken down by total adults, gender, and age group.

Confidence in Discerning True or False Information

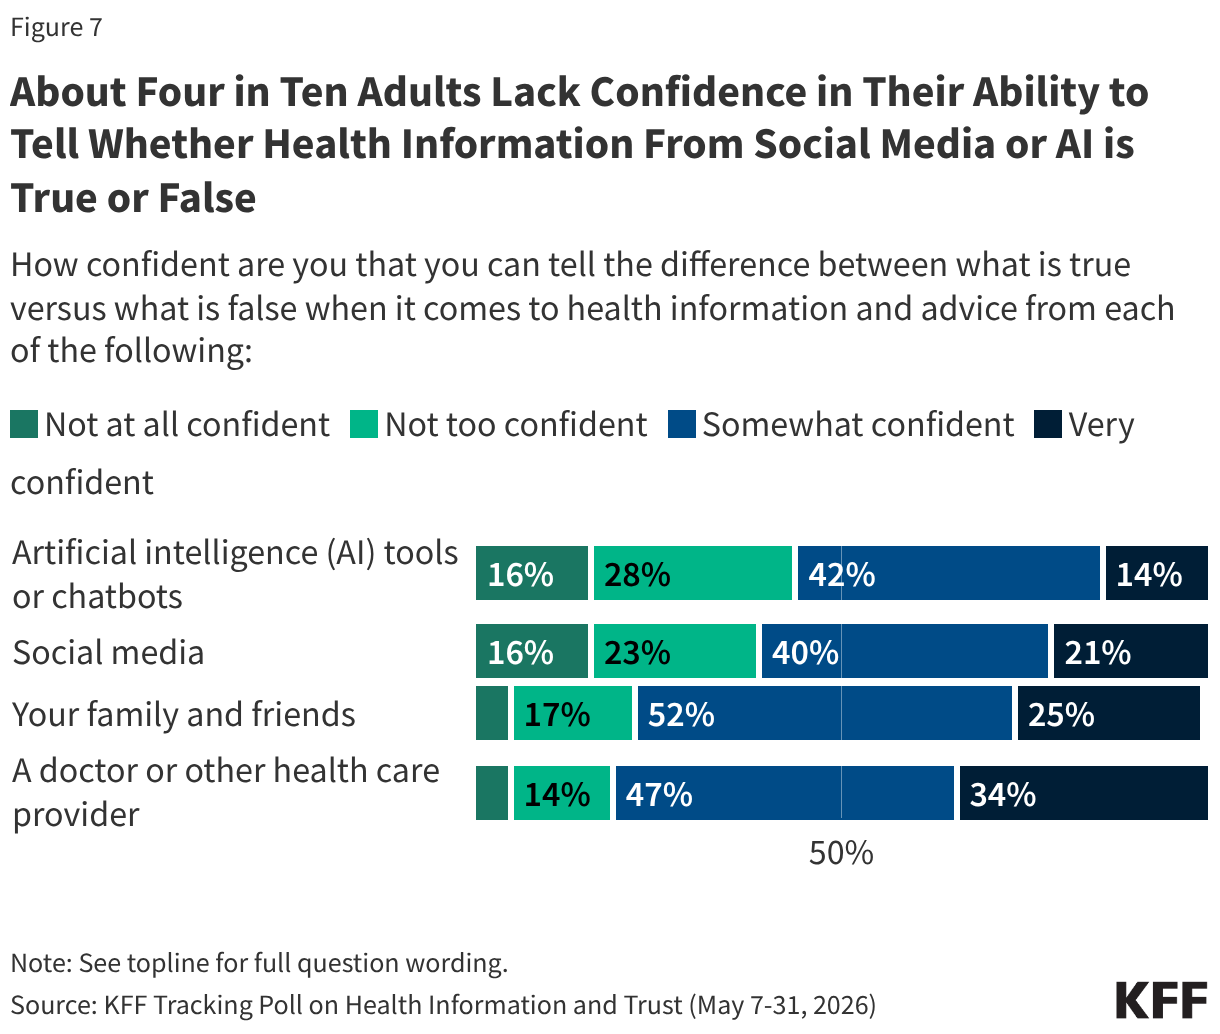
Slim majorities of adults say they are confident in their ability to tell what is true or false when it comes to health information from social media (61%) or AI chatbots (56%). In fact, roughly four in ten adults overall say they are “not too” or “not at all” confident in their ability to tell whether health information from AI chatbots (44%) or social media (39%) is true or false. Larger shares are confident when the information comes from more personal sources, with eight in ten saying they are confident they can parse information from a doctor or other health care provider (80%) or their family and friends (77%).

Stacked bar chart showing the percent of adults who said they are not at all confident, not too confident, somewhat confident, or very confident that they can tell true from false health information and advice from AI tools or chatbots, social media, family and friends, and a doctor or health care provider.

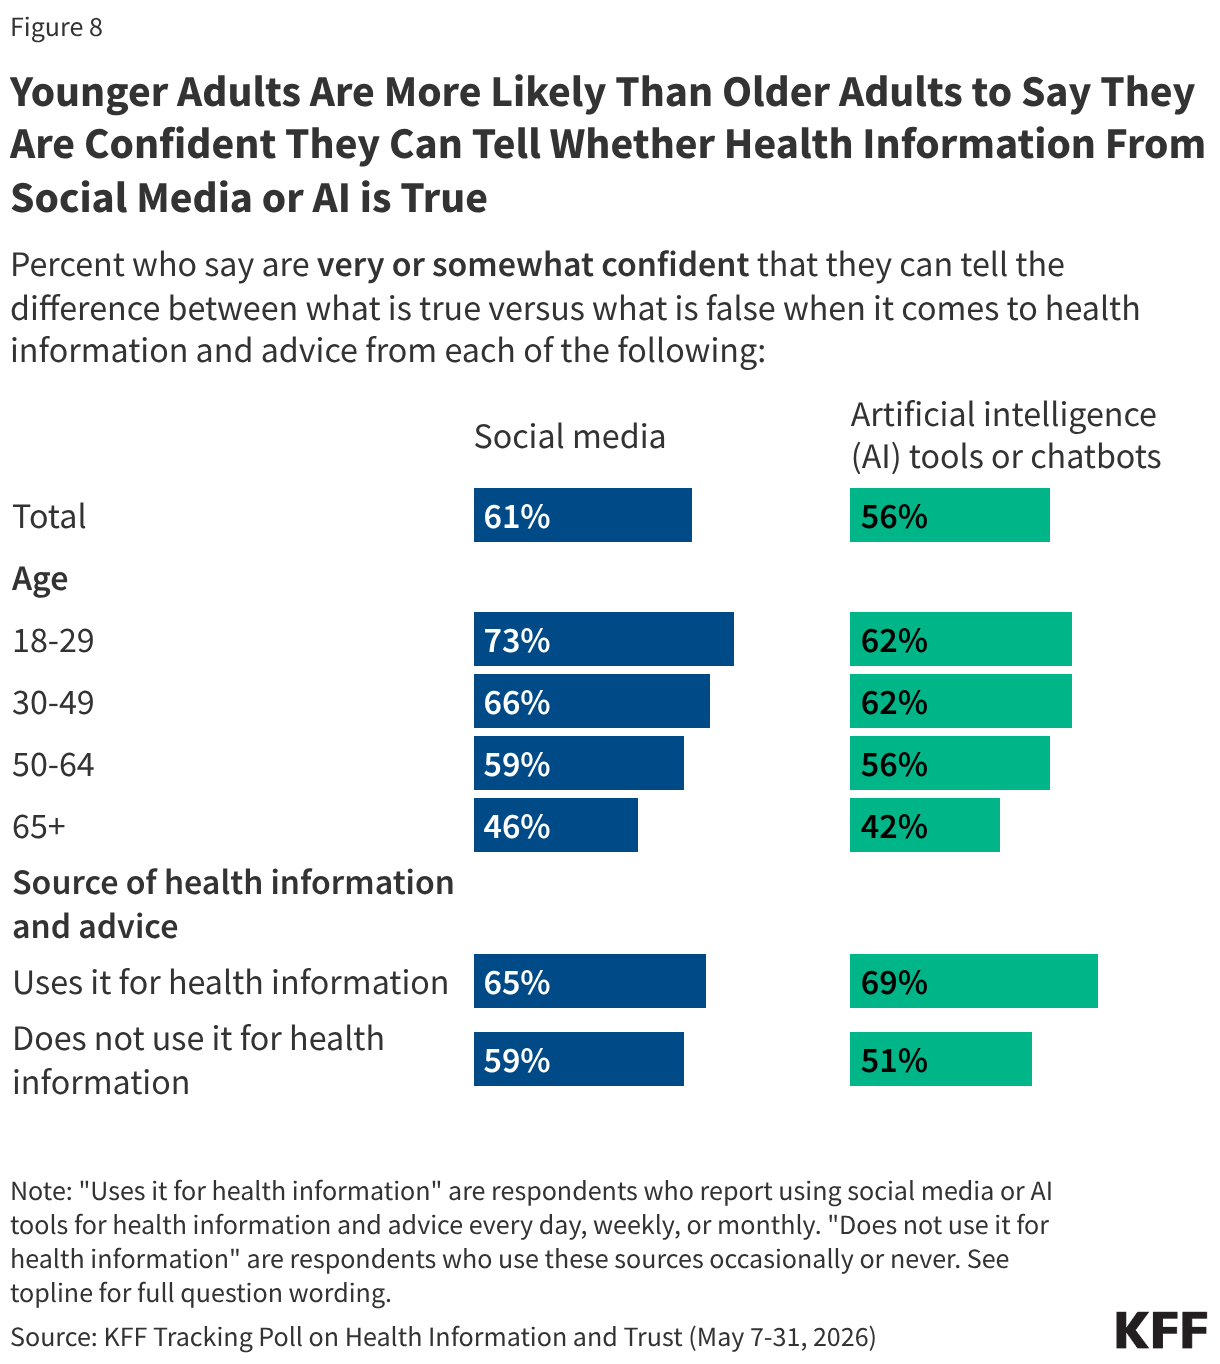
Younger adults are more likely to express confidence in their ability to tell whether health advice is true or false on both social media and AI tools or chatbots than their older counterparts. In addition to young adults, adults with a college degree or higher education and those with incomes of $90,000 or more a year are more likely than their counterparts to say they are confident they can tell the difference between true and false health information from social media and AI chatbots.

People who use AI for health advice are more likely than those who do not use it to be confident in their ability to discern what is true when using these tools. However, the difference is less pronounced when it comes to social media. Roughly seven in ten (69%) of those who use AI at least monthly are confident in being able to decipher the truth from that source, compared to half (51%) of those who use AI for health information “occasionally” or “never.” Similarly, a slightly larger share of those who use social media at least monthly say they can tell what is true or not from the health information they find on social media – around two-thirds (65%), compared to six in ten (59%) who don’t use social media for health information.

KFF’s March 2026 Tracking Poll on Health Information and Trust found that trust in AI for reliable health information was largely predicated on use, with most users saying they trust AI for health information compared to few non-users.

Grouped bar chart showing the percentage of adults who say they are very or somewhat confident they can tell true from false health information from social media and from AI tools or chatbots, broken down by total adults, age group, and whether they use each source for health information.

Following Up With Other Sources

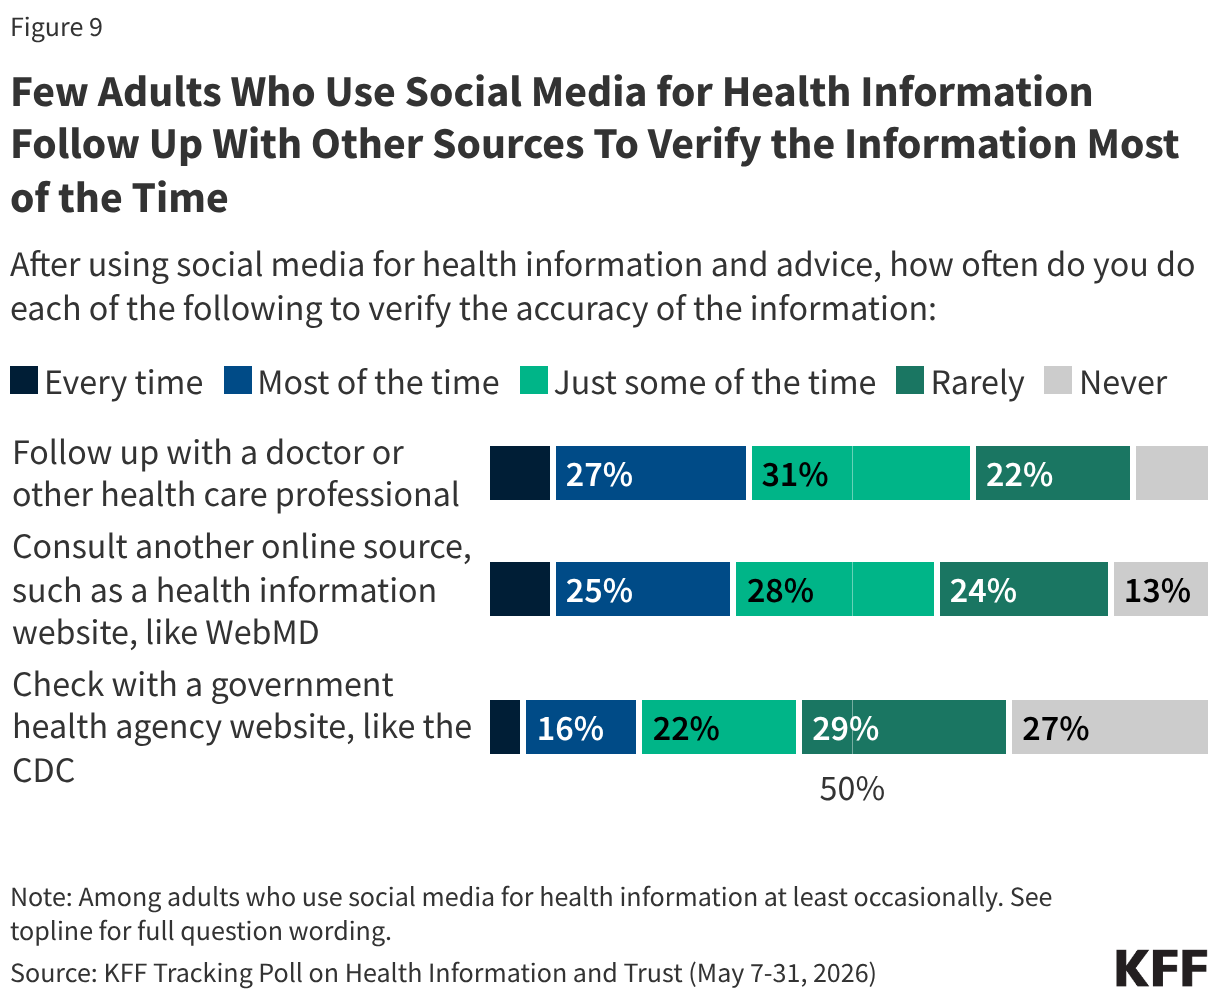
While not every health-related social media query requires a follow-up with a doctor or health care professional, few of those who seek health information on social media say they regularly consult any other source for information. Roughly a third of adults who use social media for health information and advice say they followed up with a doctor or other health care professional (36%) “every time” or “most of the time” to verify the accuracy of the information they see on social media. A similar share (35%) say they consulted another online source, such as health websites, like WebMD after using social media for information, and an even smaller share (21%) say they checked with health agency websites, like the CDC, “every” or “most of the time” after using social media for health information and advice in order to verify the accuracy of the information.

In fact, a majority of social media users say they either “some of the time,” “rarely,” or “never” followed up with a health care provider (64%), consulted another online source (65%), or checked a government health agency website (78%) after using social media for health information.

Stacked bar chart showing how often adults who use social media for health information follow up to verify accuracy, ranging from every time to never, across three verification methods: following up with a doctor or health professional, consulting another online source, and checking a government health agency website.

This KFF Tracking Poll on Health Information and Trust was designed and analyzed by public opinion researchers at KFF. The survey was conducted May 7 – 31, 2026, online and by telephone among a nationally representative sample of 2,480 U.S. adults in English (2,407) and Spanish (73).

The sample includes 1,977 who were reached through an address-based sample (ABS) and completed the survey online (1,819) or over the phone (158). An additional 503 respondents were reached through a random digit dial telephone (RDD) sample of prepaid (pay-as-you-go) cell phone numbers. Among this prepaid cell phone component, 223 were interviewed by phone and 280 were invited to the web survey via short message service (SMS). Marketing Systems Groups (MSG) provided both the ABS and RDD samples. All fieldwork was managed by SSRS of Glen Mills, PA; sampling design and weighting was done in collaboration with KFF.

Both the ABS and RDD sample frames included disproportionate stratification aimed at reaching Hispanic and non-Hispanic Black respondents. The ABS was also stratified based on model-based prediction of household-members’ party identification (Republican, Democratic, or independent).

Respondents received a $15 incentive for their participation, with interviews completed by phone receiving a mailed check and web respondents receiving an electronic gift card incentive.

In order to ensure data quality, cases were removed if they failed two or more quality checks: (1) attention check questions in the online version of the questionnaire, (2) had over 30% item nonresponse, or (3) had a length less than one quarter of the mean length by mode. Likewise, cases that were reached through ABS who reported a living in a different state than the sampled address were removed for quality assurance. Based on this criterion, 39 cases were removed.

The combined ABS and cell phone samples were weighted to match the sample’s demographics to the national U.S. adult population using data from the Census Bureau’s 2025 Current Population Survey (CPS). The combined sample was weighted by gender by age, gender by education, age by education, race/ethnicity by education, education, race, census region, population density, frequency of internet usage, recalled 2024 vote by quintiles of the county-level 2024 vote share. The weights also take into account differences in the probability of selection for each sample type (ABS and prepaid cell phone). This includes adjustment for the sample design and geographic stratification of the samples, and within household probability of selection. The population density benchmark was from the 2026 Claritas Pop-Facts Premier. The internet frequency benchmarks was from the 2025 National Public Opinion Reference Survey (NPORS) data. The county-level 2024 vote share was from CNN-provided file of 2024 election results by county

The margin of sampling error including the design effect for the full sample is plus or minus 3 percentage points. Numbers of respondents and margins of sampling error for key subgroups are shown in the table below. For results based on other subgroups, the margin of sampling error may be higher. Sample sizes and margins of sampling error for other subgroups are available by request. Sampling error is only one of many potential sources of error and there may be other unmeasured error in this or any other public opinion poll. The following questions included in this survey were designed, analyzed, and paid for by KFF. The demographic questions included in this study were developed and funded jointly by CNN and KFF, with each organization having independent editorial control over its portion of the survey. KFF Public Opinion and Survey Research is a charter member of the Transparency Initiative of the American Association for Public Opinion Research.

GroupN (unweighted)M.O.S.E.
Total2,480± 3 percentage points
Race/Ethnicity 
White, non-Hispanic1,355± 3 percentage points
Black, non-Hispanic435± 6 percentage points
Hispanic420± 7 percentage points
Age  
18-29399± 7 percentage points
30-49888± 4 percentage points
50-64590± 5 percentage points
65+556± 6 percentage points
Party ID  
Democrats774± 5 percentage points
Independents876± 5 percentage points
Republicans607± 5 percentage points