KFF designs, conducts and analyzes original public opinion and survey research on Americans’ attitudes, knowledge, and experiences with the health care system to help amplify the public’s voice in major national debates.
Episode 20, AI Series: Walk into the emergency room at Israel’s largest hospital and the first clinician to take your history may be an AI avatar — with a physician signing off on every recommendation. Israel’s Sheba Medical Center is building what could become the first fully AI-based hospital by 2030. Dr. Eyal Zimlichman, Sheba’s Chief Transformation Officer, Chief Innovation Officer and Chief AI officer, talks with Chip about what that means for patients. During their conversation, Dr. Zimlichman argues that in the future, doctors will “be much more humane than the doctors of the present…because if we’re not able to achieve that, then there’s really no difference between the AI and the physician…we will be able to compete with the AI in terms of humanity.”
Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.
Chief Transformation Officer, Chief Innovation Officer, and Chief AI Officer, Sheba Medical Center; Founder, ARC Innovation
Eyal Zimlichman, MD, is a physician, healthcare executive, and researcher specializing in healthcare quality, value, and patient safety. In the separate roles of Chief Transformation Officer, Chief Innovation Officer, and Chief AI Officer at Sheba Medical Center at Sheba Medical Center—Israel’s largest hospital—he drives efforts to make care more patient-centered, efficient, and equitable, and founded ARC (Accelerate, Redesign, Collaborate), Sheba’s global platform for advancing digital health and AI through collaboration with healthcare institutions, industry, and startups. His leadership has earned international recognition, including being named a Chief Transformation Officer to Know by Becker’s Hospital Review in 2023 and 2024. He previously served as Sheba’s Chief Medical Officer and, before that, its Chief Quality Officer. Dr. Zimlichman holds a Master of Science in Healthcare Management from the Harvard T.H. Chan School of Public Health and earned his MD from the Technion – Israel Institute of Technology.
This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.
The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.
Medicaid State Fact Sheets
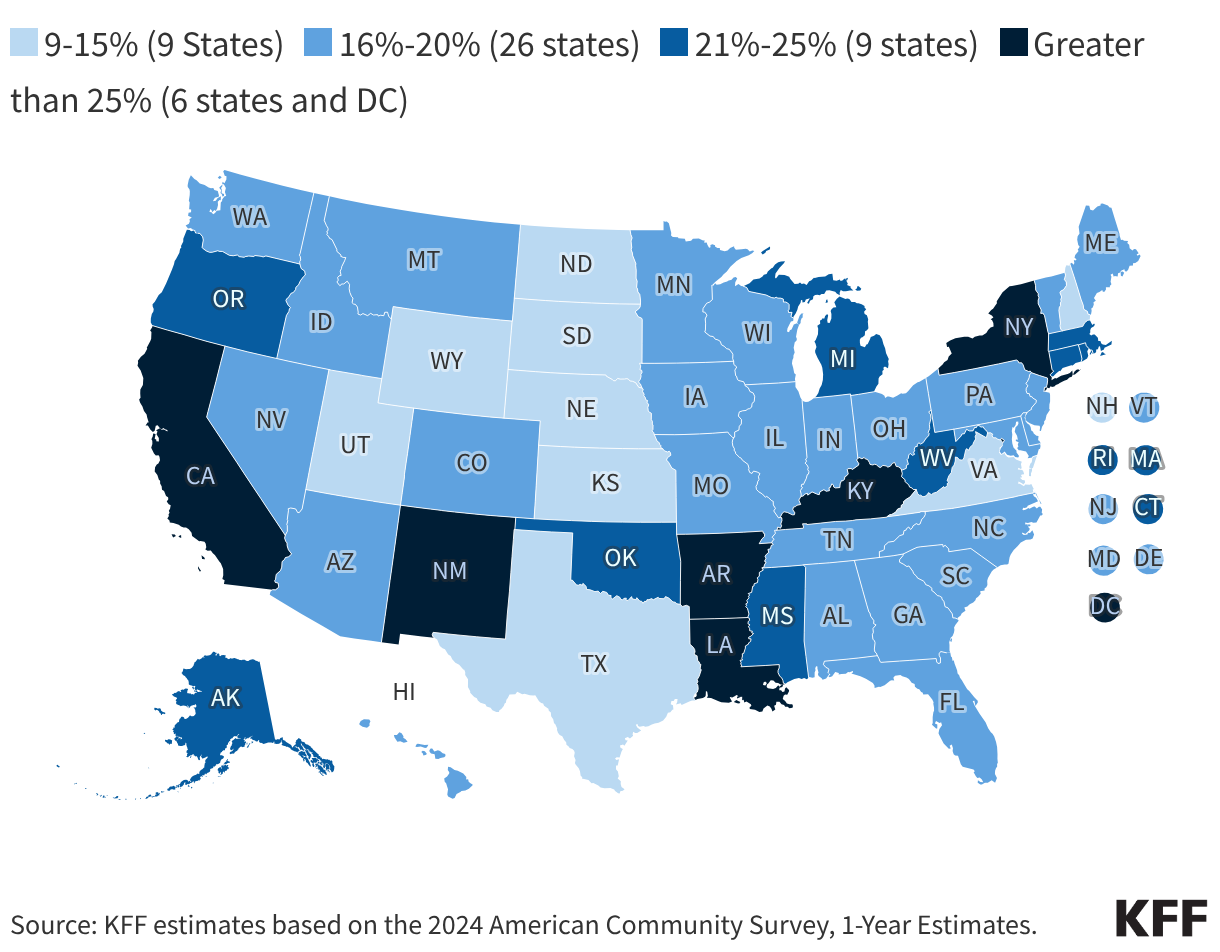
Medicaid and CHIP provide health and long-term care coverage to millions of low-income children and adults in the United States. The programs are jointly financed by the federal government and states and are administered by states within broad federal rules. As a result, programs vary widely across states in how many and which residents they cover and how much they spend. These differences reflect state policy choices, such as whether to adopt the ACA Medicaid expansion or set income limits above federal minimums for certain groups, as well as differences in demographic characteristics of state populations. These fact sheets provide key data on Medicaid programs in every state.
Click a state’s tooltip in the map or the state name in the table below to view the fact sheets.
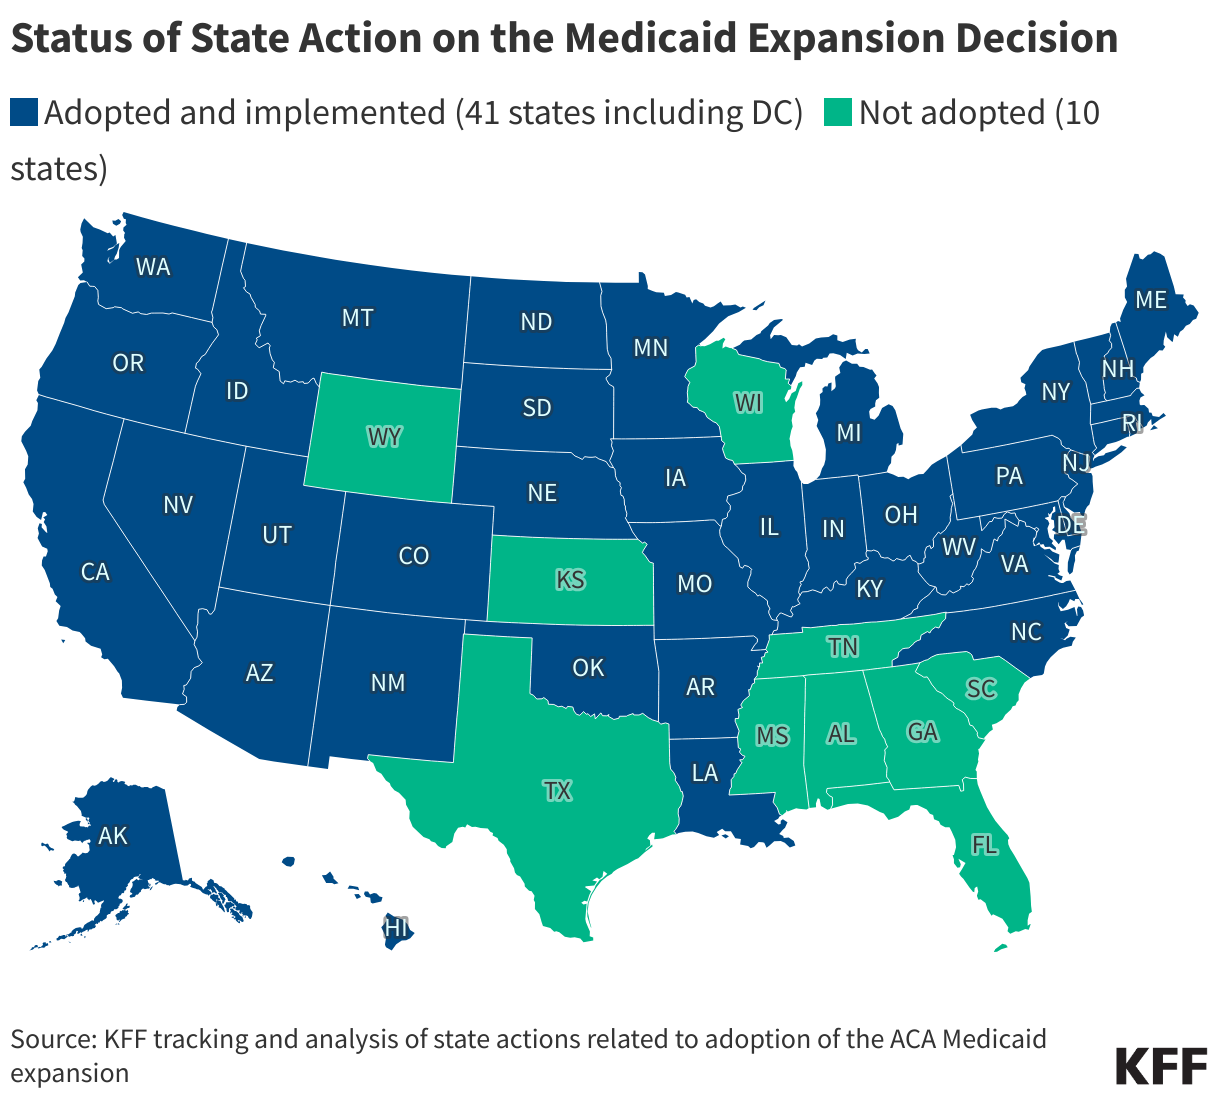
The Affordable Care Act’s (ACA) Medicaid expansion expanded Medicaid coverage to nearly all adults with incomes up to 138% of the Federal Poverty Level ($21,597 for an individual in 2025) and provided states with an enhanced federal matching rate (FMAP) for their expansion populations.
To date, 41 states (including DC) have adopted the Medicaid expansion and 10 states have not adopted the expansion. Current status for each state is based on KFF tracking and analysis of state expansion activity.
These data are also available in a table format. The map may be downloaded as a Powerpoint.
Status of State Action on the Medicaid Expansion Decision
* State has a trigger law that would end expansion coverage or require states to take steps to mitigate increases in state costs if federal funding for the expansion is reduced.
This table tracks current state actions related to adoption and implementation ofthe Affordable Care Act (ACA) Medicaid expansion. Information about original adoption and implementation of the ACA expansion can be found on State Health Facts. For non-expansion states, we include recent activity related to debate about adopting the ACA expansion. Actions captured in the tracker include legislative actions (passage of bills in at least one legislative chamber or committee), executive actions (Governor’s budget proposal, executive orders, or other significant announcements), and voter-led actions (progress toward ballot initiatives). We also mention some limited coverage expansions that would not qualify as full ACA Medicaid expansions and would not qualify for enhanced federal matching funds. For expansion states, we include recent actions that would place limits or new requirements on the expansion population, especially through Section 1115 waivers.
^State has recent activity related to “trigger” laws tied to the share of federal funding. South Dakota and West Virginia are or were considering action to put a trigger law in place. In Virginia, a budget amendment to remove automatic termination of the expansion from the state’s trigger law and instead require a legislative committee to develop recommendations on ways to adjust to the loss of federal funding was introduced but not included in the final budget. Proposals to remove or scale back trigger laws have been introduced in Illinois and North Carolina.
Policy Tracker: Exceptions to State Abortion Bans and Early Gestational Limits
Last updated on October 16, 2026
19
states have abortion bans or early gestational limits in effect
5
states have nohealth exception
8
states have no rape or incest exception
11
states have no fatal fetal anomaly exception
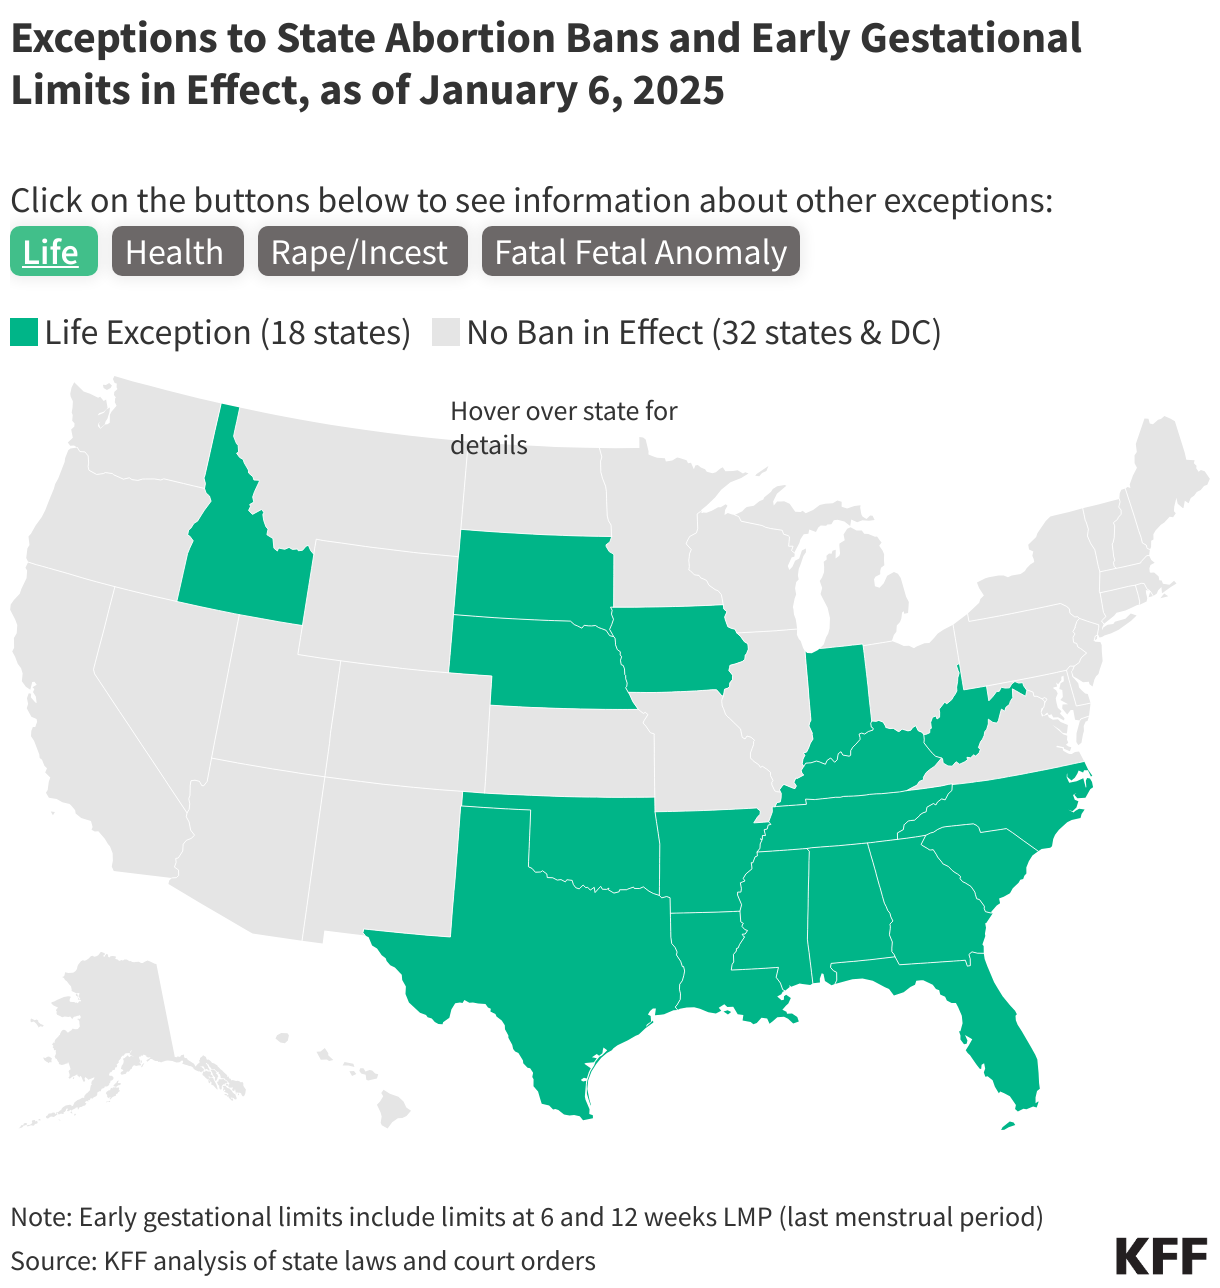
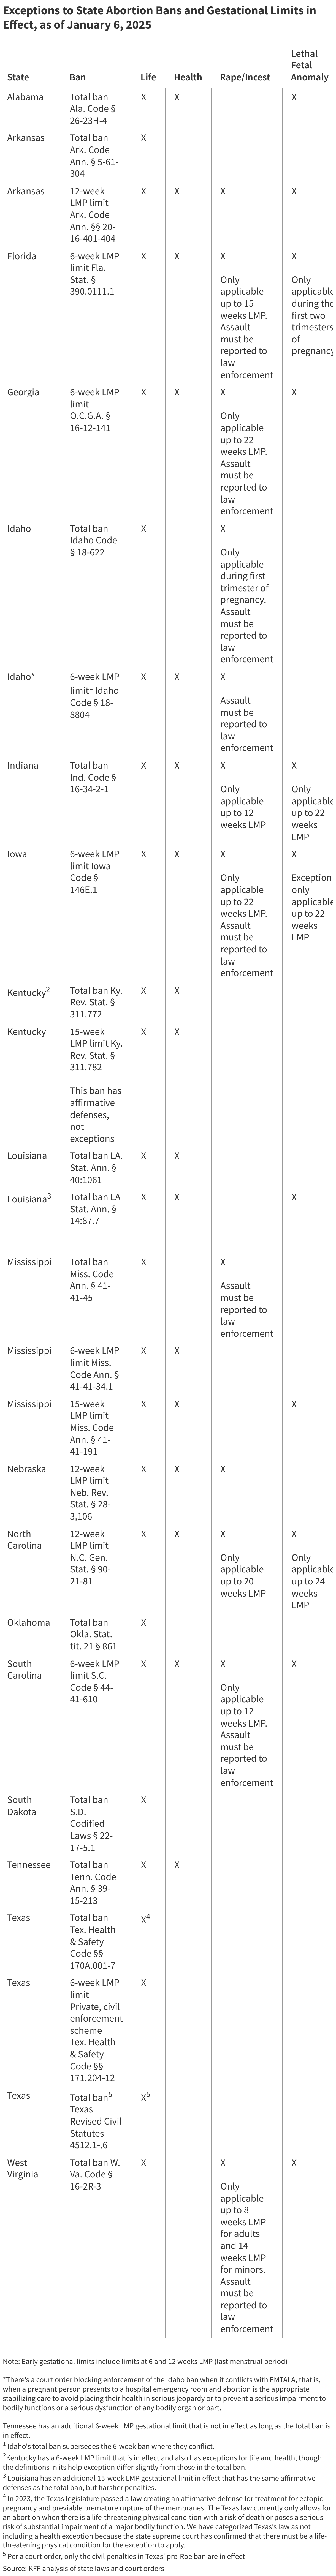
The provision of abortion is currently banned in 13 states and 6 states have early gestational limits between 6 weeks and 12 weeks in effect. Nearly all of these bans include exceptions, which generally fall into four categories: to prevent the death of the pregnant person, when there is risk to the health of the pregnant person, when the pregnancy is the result of rape or incest, and when there is a lethal fetal anomaly. Almost all states with a health exception limit it to conditions affecting physical health, with some going further by explicitly excluding emotional or psychological conditions. Alabama is currently the only state with an abortion ban or early gestational limit in place that includes an exception for mental health within its broader health exception. Some states have more than one abortion ban or restriction in place. The maps below illustrate the exceptions in each state’s most restrictive gestational limit or total ban. For details hover over each state to read the rollover.
Exceptions to State Abortion Bans and Early Gestational Limits in Effect, as of October 16, 2026
Click on the buttons below to see information about other exceptions:
Life
Health
Rape/Incest
Fatal Fetal Anomaly
Early gestational limits include limits at 6 and 12 weeks LMP (last menstrual period)
KFF analysis of state laws and court orders
Exceptions to State Abortion Bans and Early Gestational Limits in Effect, as of October 16, 2026
Click on the buttons below to see information about other exceptions:
Life
Health
Rape/Incest
Fatal Fetal Anomaly
Early gestational limits include limits at 6 and 12 weeks LMP (last menstrual period)
There’s a court order blocking enforcement of the Idaho ban, at St. Luke's Hospitals, when it conflicts with EMTALA, that is, when a pregnant person presents to a hospital emergency room and abortion is the appropriate stabilizing care to avoid placing their health in serious jeopardy or to prevent a serious impairment to bodily functions or a serious dysfunction of any bodily organ or part. There is also a court order blocking enforcement of Idaho’s ban against Dr. Stacy T. Seyb when, in his good-faith medical judgment, continuing the pregnancy poses a non-negligible risk of serious and lasting harm to the pregnant person’s health.
KFF analysis of state laws and court orders
Exceptions to State Abortion Bans and Early Gestational Limits in Effect, as of October 16, 2026
Click on the buttons below to see information about other exceptions:
Life
Health
Rape/Incest
Fatal Fetal Anomaly
Early gestational limits include limits at 6 and 12 weeks LMP (last menstrual period)
KFF analysis of state laws and court orders
Exceptions to State Abortion Bans and Early Gestational Limits in Effect, as of October 16, 2026
Click on the buttons below to see information about other exceptions:
Life
Health
Rape/Incest
Fatal Fetal Anomaly
Early gestational limits include limits at 6 and 12 weeks LMP (last menstrual period)
KFF analysis of state laws and court orders
Exceptions to State Abortion Bans and Gestational Limits in Effect, as of October 16, 2026
Early gestational limits include limits at 6 and 12 weeks LMP (last menstrual period)
*Almost all states with health exceptions limit them to conditions affecting physical health, with some going further and explicitly precluding emotional or psychological health conditions. Alabama, the only state that includes mental health concerns in its health exception, requires a psychiatrist to diagnose the pregnant person with a “serious mental illness” and document it is likely the person will engage in behavior that could result in their death or the death of the fetus that due to their mental health condition.
1There’s a court order blocking enforcement of the Idaho ban, at St. Luke's Hospitals, when it conflicts with EMTALA, that is, when a pregnant person presents to a hospital emergency room and abortion is the appropriate stabilizing care to avoid placing their health in serious jeopardy or to prevent a serious impairment to bodily functions or a serious dysfunction of any bodily organ or part.
2On August 13, 2026, in Seyb v. Members of the Idaho Board of Medicine, an Idaho District Court held that the Idaho Defense of Life Act and Fetal Heartbeat Act are unconstitutional because they lack an exception to protect a pregnant person’s health, including mental health. The Idaho District Court enjoined the Ada County Prosecuting Attorney and the Idaho Attorney General from prosecuting cases where a physician, in their good-faith medical judgment, determines that continuing the pregnancy poses a non-negligible risk of serious and lasting harm to the pregnant person’s health, including their mental health. The defendants appealed and moved for an emergency stay on August 18, 2026. On August 25, 2026, the district court narrowed the injunction to bar enforcement of both laws only against Dr. Stacy T. Seyb, for abortions he performs to preserve a pregnant person’s health(including mental health).
3 Idaho's total ban supersedes the 6-week ban where they conflict.
4 On March 5, 2026, a Superior Court issued a permanent injunction that blocked enforcement of Indiana’s ban on the provision of abortion against individuals whose sincerely held religious beliefs require them to receive an abortion. This decision has been appealed to the Indiana Supreme Court, and oral arguments were held on September 10, 2026. No final decision has been issued yet.
5Kentucky has a 6-week LMP limit that is in effect and also has exceptions for life and health, though the definitions in its health exception differ slightly from those in the total ban.
6 Louisiana has an additional 15-week LMP gestational limit in effect that has the same affirmative defenses as the total ban, but harsher penalties.
7 On March 21, 2023, the Oklahoma Supreme Court held "a woman has an inherent right to choose to terminate her pregnancy if at any point in the pregnancy, the woman's physician has determined to a reasonable degree of medical certainty or probability that the continuation of the pregnancy will endanger the woman's life due to the pregnancy itself or due to a medical condition that the woman is either currently suffering from or likely to suffer from during the pregnancy."
8 On March 20, 2026, Governor Rhoden signed HB 1257 which includes excluded from the defintion of abortion: (1)medical treatment that is provided to a pregnant female and results in the accidental or unintentional death of the unborn child; (2)treatment to resolve a miscarriage; (3) the treatment or removal of an ectopic pregnancy; (4)the removal from the uterus of a deceased unborn child; or (5)any medical procedure performed for the purpose of saving the life or preserving the health of the unborn child.
9Tennessee has an additional 6-week LMP gestational limit that is not in effect as long as the total ban is in effect.
10 Per a court order, only the civil penalties in Texas' pre-Roe ban are in effect.
KFF analysis of state laws and court orders
Green Card Processing Backlogs for Refugees and Asylees Could Have Implications for Health Coverage and Care
The 2025 reconciliation law eliminated access to federally funded health coverage for refugees and asylees without a green card as well as several other groups of lawfully present immigrants. Refugees and asylees can apply for Lawful Permanent Resident status (LPR status, or a green card) after one year in the country or one year after being granted asylum. Because the 2025 reconciliation law largely limits eligibility for federally funded coverage to lawfully present immigrants with LPR status, how quickly U.S. Citizenship and Immigration Services (USCIS) processes these applications directly affects whether refugees and asylees can keep or gain access to Medicaid, the Children’s Health Insurance Program (CHIP), subsidized Affordable Care Act (ACA) Marketplace, and Medicare coverage.
This data note highlights changes in green card (I-485) application processing for refugees and asylees between fiscal year (FY) 2021 and FY2025, as well as across the first three quarters of FY2025 to FY2026 (since FY2026 data are only available through the third quarter). It discusses the implications of these trends for access to federally funded health coverage following eligibility changes under the 2025 reconciliation law. It is based on KFF analysis of USCIS data.
In this analysis, we find a decrease in USCIS completion of applications for adjustment to LPR status for refugees and asylees between FY2025 and FY2026. While some of the decreases in application completions could be due to fewer humanitarian migrants being admitted into the U.S. in recent years, we find that the number of applications completed by USCIS as a share of all applications fell between FY2025 and FY2026 and the average processing time for applications increased during the same time period. As of June 30, 2026, there were over 275,000 pending green card applications from refugees and asylees awaiting a decision from USCIS, and between FY2025 and FY2026, the average processing time for applications had increased from 7.8 months to 13.3 months for refugees and from 10.7 months to 19.9 months for asylees. As a result, many refugees and asylees who have already applied for a green card will be left without access to federally funded health coverage for potentially long periods of time as they wait for USCIS to process their green card applications.
Changes in Health Coverage for Refugees and Asylees
Since 1980, the U.S. has had a formal system for admitting refugees and asylees—individuals and their families who are unable to return to their country of nationality due to a well-founded fear of persecution for certain protected reasons. The right to seek asylum is rooted in international law, and the system reflects the U.S.’s longstanding inclusion of humanitarian protection as a core principle of immigration law. Refugees and asylees are generally fleeing from unsafe conditions and arrive to the U.S. with few to no resources, with many experiencing traumatic experiences in their countries of origin and/or during their journey to the U.S. The U.S. historically provided refugees and asylees access to assistance with food, housing, and health care upon arrival to the country as well as other time-limited services to support their transition to the U.S. Since taking office, the Trump administration has taken steps to significantly reduce the entry of refugees and asylees into the U.S., including by pausing refugee applications, setting the lowest ceiling for refugee admissions on record, and effectively closing the southern border to most migrants, including asylum seekers.
Under federal law, refugees and asylees (i.e. those who have officially been granted asylum) can apply for adjustment to LPR status once they have been physically present in the U.S. for at least one year. They apply by filling out Form I-485, “Application to Register Permanent Residence or Adjust Status.” Asylum seekers whose asylum applications are still awaiting approval are not considered asylees and are not eligible to apply for LPR status regardless of their length of stay in the country.
The 2025 reconciliation law eliminated refugees’ and asylees’ longstanding access to federally funded health coverage as well as other public assistance programs. Most lawfully present immigrants, including most LPRs, must wait five years after getting a “qualified” immigration status before they can enroll in federally funded coverage such as Medicaid and CHIP. Under longstanding policy, refugees and asylees previously were exempt from this waiting period if they met income and other state eligibility requirements. They could also enroll in subsidized ACA Marketplace coverage and Medicare if otherwise eligible. However, the 2025 reconciliation law eliminates eligibility for Medicaid and CHIP (except in states that use a Medicaid and/or CHIP option to cover lawfully residing children and pregnant people), subsidized Marketplace coverage, and Medicare for refugees and asylees without a green card, as well as certain other groups of lawfully present immigrants. The Medicaid and CHIP restrictions took effect October 1, 2026, with restrictions on subsidized Marketplace and Medicare coverage fully taking effect in January 2027. The Congressional Budget Office estimates that the law’s eligibility restrictions for lawfully present immigrants will lead to about 1.4 million people becoming uninsured by 2034.
Trends in Processing Green Card Applications for Refugees and Asylees
The number of I-485 applications received for adjustment to LPR status for both refugees and asylees increased between FY2021 and FY2025, but applications received for asylees dropped between FY2025 and FY2026. Between FY2021 and FY2025, I-485 applications received for adjustment to LPR status increased by 274% (22,906 to 85,743) for refugees and by 68% (44,837 to 75,292) for asylees. Lower numbers of I-485 applications received from refugees and asylees in FY2021 could reflect COVID-19-related reductions in the entry of migrants into the U.S. Between the first three quarters of FY2025 and FY2026, I-485 applications received for refugees continued to increase but at a lower rate of about 10% (59,754 to 66,013) and decreased by about 32% (58,682 to 40,344) for asylees. This pattern could reflect that the Trump administration lowered the refugee admissions cap from 125,000 in FY2025 to 7,500 for FY2026. Additionally, the Biden and Trump administrations effectively closed the border to individuals seeking asylum starting in 2024.
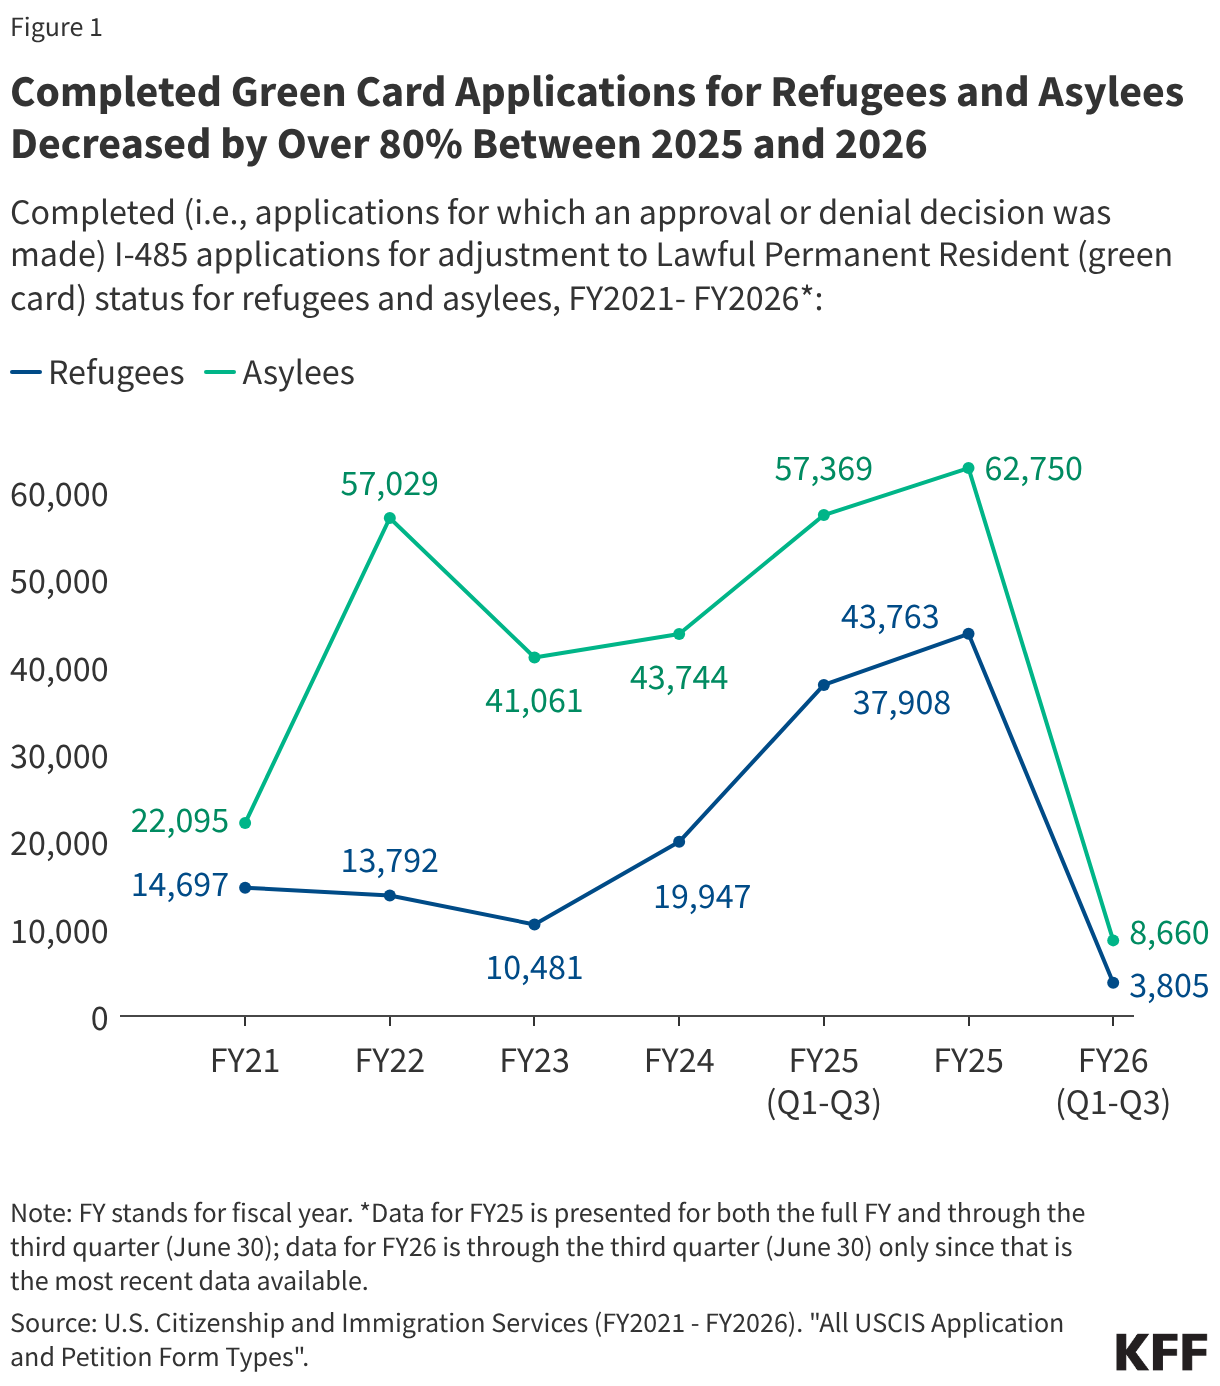
While the number of applications completed by USCIS for both refugees and asylees increased between FY2021 and FY2025, they decreased significantly between FY2025 and FY2026 (Figure 1). Between FY2021 and FY2025, completed I-485 applications, i.e., applications for which an approval or denial decision was made by USCIS, increased by 198% for refugees (14,697 to 43,763) and by 184% for asylees (22,095 to 62,750). However, between the first three quarters of FY2025 and FY2026, I-485 applications completed by USCIS decreased by about 90% (37,908 to 3,805) for refugees and by about 85% (57,369 to 8,660) for asylees.
Completed Green Card Applications for Refugees and Asylees Decreased by Over 80% Between 2025 and 2026
Completed (i.e., applications for which an approval or denial decision was made) I-485 applications for adjustment to Lawful Permanent Resident (green card) status for refugees and asylees, FY2021- FY2026*:
FY stands for fiscal year. *Data for FY25 is presented for both the full FY and through the third quarter (June 30); data for FY26 is through the third quarter (June 30) only since that is the most recent data available.
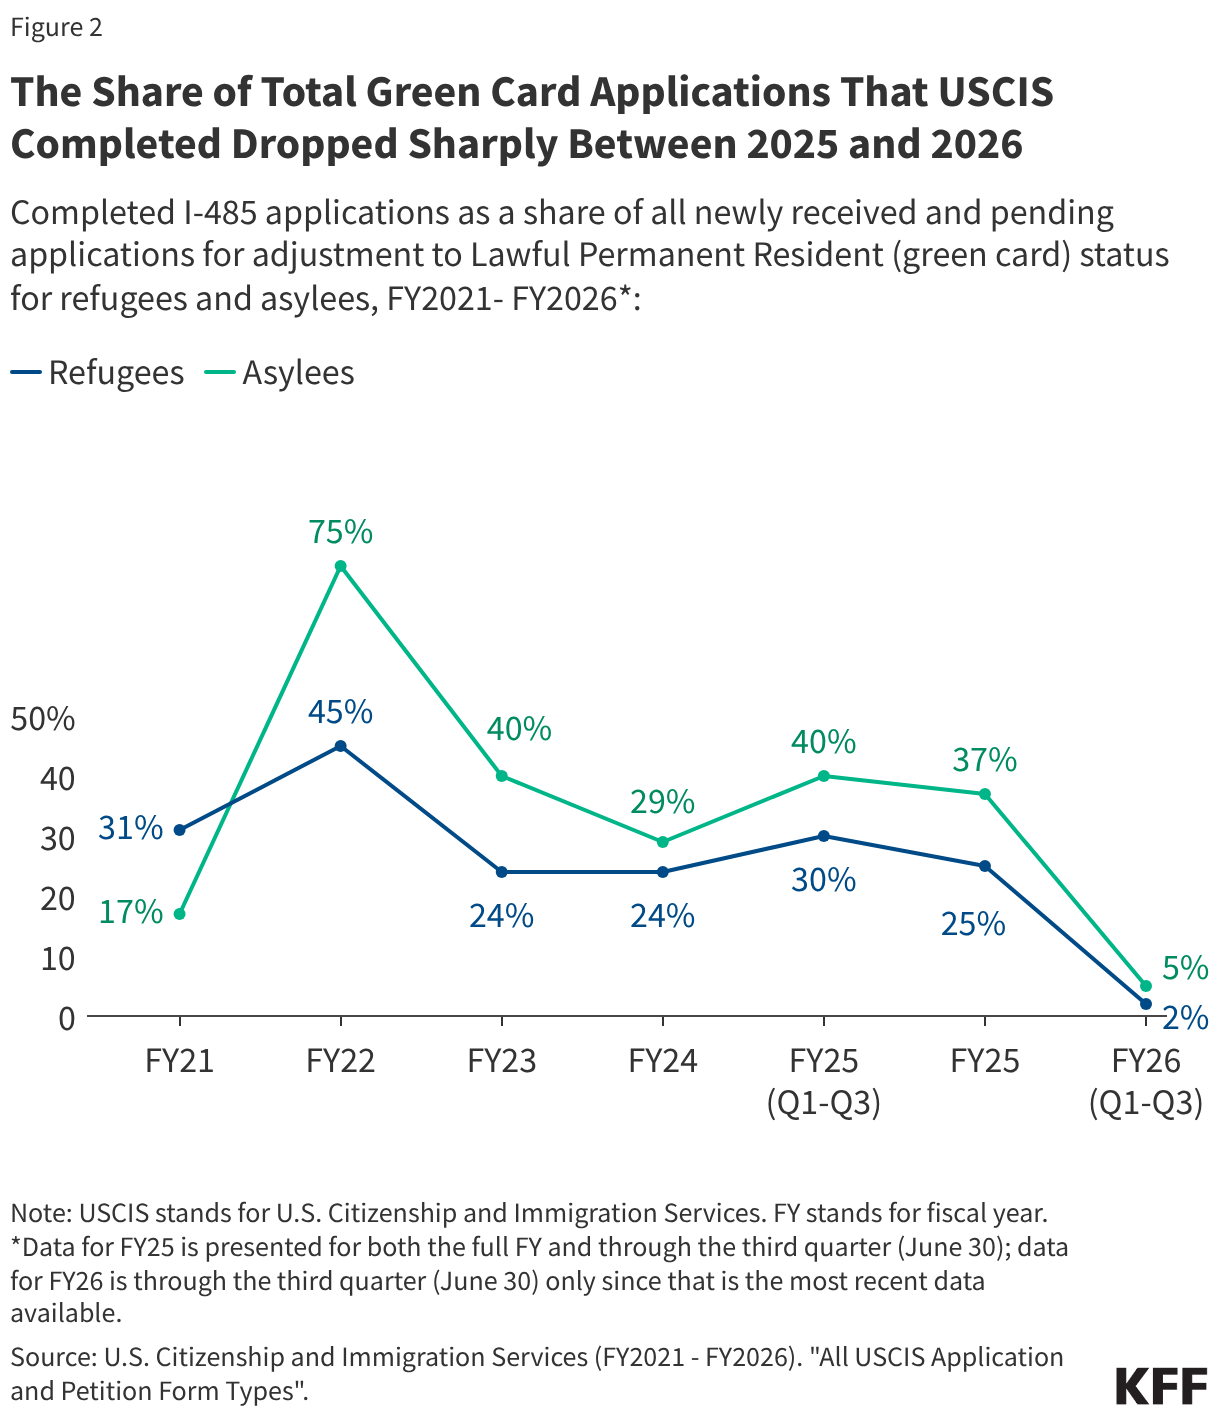
The percentage of completed applications as a share of all applications for refugees and asylees dropped sharply between FY2025 and FY2026 (Figure 2). Between FY2021 and FY2025, the percentage of I-485 applications completed by USCIS as a share of all applications (i.e., newly received and pending applications)decreased from 31% to 25% for refugees and increased from 17% to 37% for asylees. However, between the first three quarters of FY2025 and FY2026, completed I-485 applications as a share of all applications decreased sharply from 30% to just 2% for refugees and from 40% to just 5% for asylees.
The Share of Total Green Card Applications That USCIS Completed Dropped Sharply Between 2025 and 2026
Completed I-485 applications as a share of all newly received and pending applications for adjustment to Lawful Permanent Resident (green card) status for refugees and asylees, FY2021- FY2026*:
USCIS stands for U.S. Citizenship and Immigration Services. FY stands for fiscal year. *Data for FY25 is presented for both the full FY and through the third quarter (June 30); data for FY26 is through the third quarter (June 30) only since that is the most recent data available.
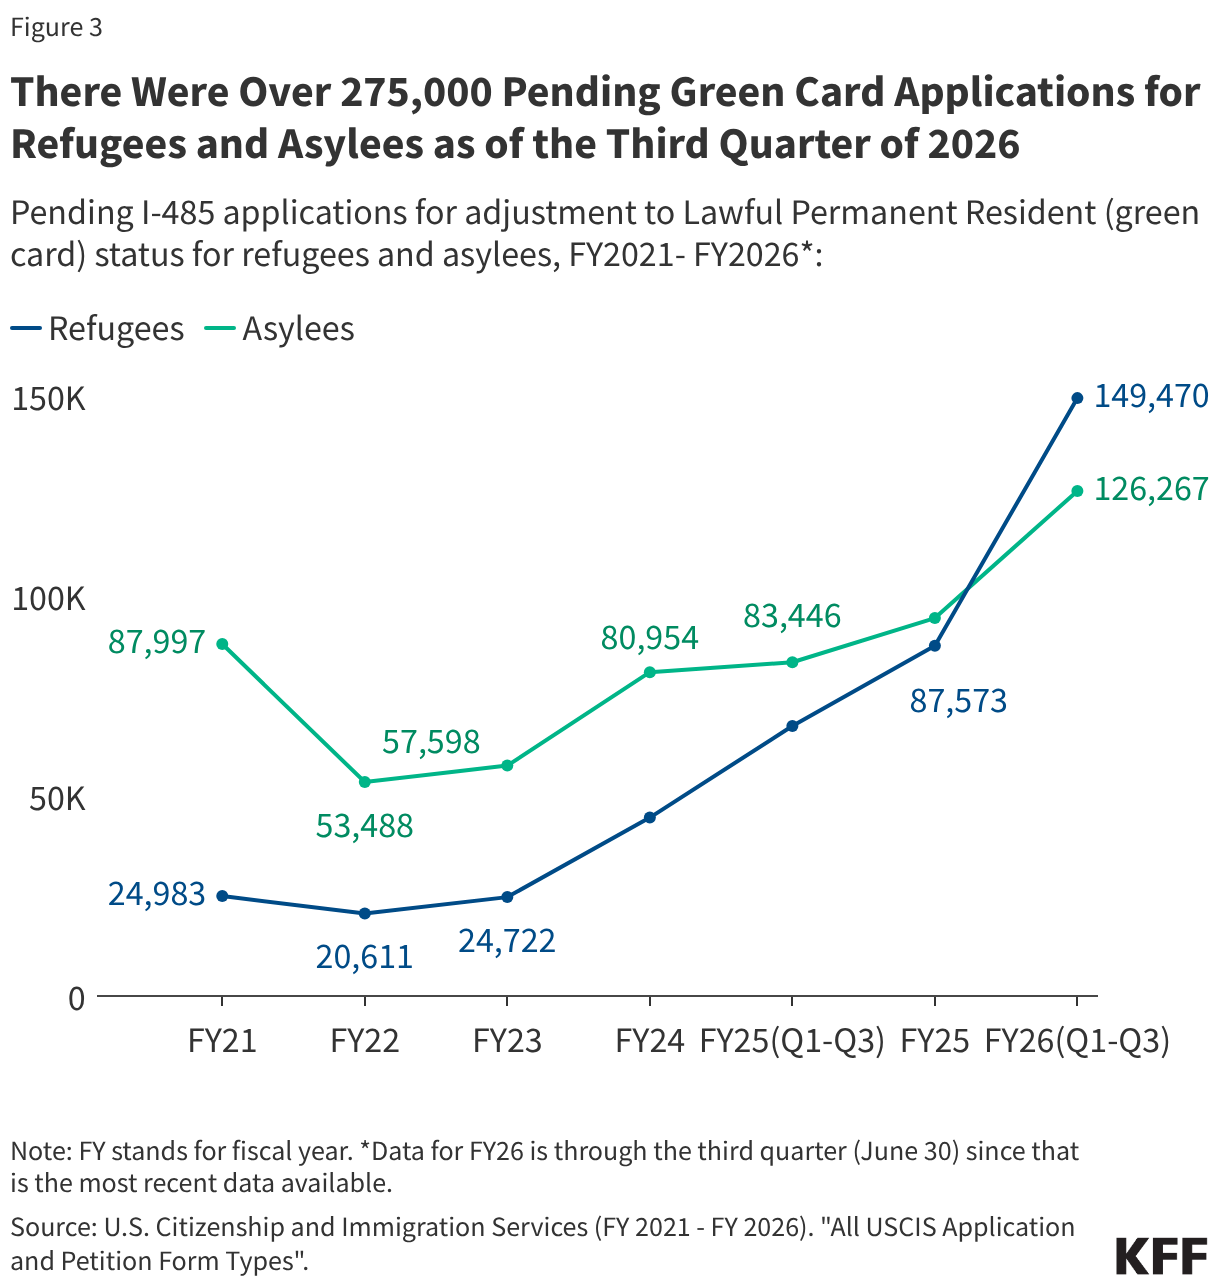
At the same time, the number of pending green card applications for refugees and asylees grew to over 275,000 as of the third quarter of FY2026, and application processing times increased between 2025 and 2026. The number of I-485 applications pending a decision from USCIS increased 251% for refugees, from 24,983 as of the end of FY2021 to 87,573 as of the end of FY2025, and by about 7% for asylees, from 87,997 as of the end of FY2021 to 94,482 as of the end FY2025 (Figure 3). Between the third quarter of FY2025 and the third quarter of FY2026, pending applications from refugees increased by 121% (67,502 to 149,470) and from asylees by 51% (83,446 to 126,267), for a total of 275,737 pending applications as of June 30, 2026. This number is expected to continue to increase by the end of FY2026. Further, reflecting the decrease in completed applications, the average processing time for green card applications increased from 7.8 months to 13.3 months for refugees, and from 10.7 months to 19.9 months for asylees between the first three quarters of FY2025 and FY2026. Within FY2026, the processing time for green card applications from refugees and asylees has increased each quarter, more than doubling from 7.6 months in Q1 to 17.6 months in Q3 for refugees and from 12.1 months in Q1 to 25.6 months in Q3 for asylees.
There Were Over 275,000 Pending Green Card Applications for Refugees and Asylees as of the Third Quarter of 2026
Pending I-485 applications for adjustment to Lawful Permanent Resident (green card) status for refugees and asylees, FY2021- FY2026*:
FY stands for fiscal year. *Data for FY26 is through the third quarter (June 30) since that is the most recent data available.
Originally published on October 1, 2026, this policy watch has been updated on October 15, 2026 to reflect additional developments and updated measles death reports from Pennsylvania.
Overview
Amid the largest U.S. measles epidemic in decades, and one that threatens the country’s measles elimination status, a controversy has emerged regarding how to count deaths from measles. From August through October 15th this year, Pennsylvania has reported a total of sixmeasles deaths had occurred in the state but so far, the Centers for Disease Control and Prevention (CDC) has recognized only two these in its official measles statistics. CDC announced in early September that it would change how it counts measles deaths, no longer relying solely on reports from state health departments and instead looking to official death records as tracked by the National Center for Health Statistics (NCHS, a sub-agency within CDC). This new CDC policy of relying on NCHS-based mortality data to count measles deaths marks a departure from historical norms and processes that have accepted measles death reports from state health departments.
This Policy Watch reviews how measles deaths are typically determined, how these deaths are counted by the federal government and the role of two distinct but related federal public health surveillance systems at the center of the controversy – the CDC’s Nationally Notifiable Diseases Surveillance System (NNDSS) and NCHS’ National Vital Statistics System (NVSS). NNDSS and NVSS are separate public health surveillance systems with their own strengths and limitations: with NNDSS focused on real-time disease tracking that at times can also provide preliminary mortality information, while NVSS is focused on collecting longer-term, retrospective data on deaths and providing final determinations regarding the cause(s) of death though not necessarily designed for real-time tracking. These two systems are complements, but one does not entirely replace the other.
The Secretary of Health and Human Services (HHS) Robert F. Kennedy, Jr. initially objected to Pennsylvania’s classification of these deaths as measles-associated, saying Shapiro’s announcement was “premature” and suggesting the deaths “may even have been altogether fabricated.” CDC staff initially accepting the state’s death reports, though Kennedy later asked the CDC Director to remove any reference to those measles deaths on the CDC website. After the coroner in Lancaster County confirmed that measles was a contributing cause to the reported deaths, on September 4 Kennedy recognized measles as the cause for “only the second infant’s death” and stated: “The National Center for Health Statistics does not currently have any death records from 2026 that indicate measles is the underlying cause” but indicated CDC will update its measles death statistics upon receipt of such records. On September 14, a CDC spokesperson stated the agency had changed how it will count measles deaths in its official statistics, and going forward CDC would “report measles deaths if and when the National Center for Health Statistics reports measles as the underlying cause of death.” The next day, PA DOH reported two additional measles-associated deaths, bringing the state’s own total to four. However, at present the CDC measles outbreak tally reports two deaths for 2026, with a note saying: “This number is subject to change; CDC will update its reporting as additional information becomes available and relevant reviews are completed.” On September 30, the Pennsylvania Department of Health confirmed a fifth death and a sixth death was announced by the Franklin County Coroner on October 12.
Two Systems with Different Purposes
The dispute around reporting measles deaths has brought new focus to two separate federal public health surveillance systems: the Nationally Notifiable Disease Surveillance System (NNDSS) and the National Vital Statistics System (NVSS). Each of these has a long history, dating back to the early 20th century, but serves different purposes. These systems are described below (see Table 1).
Nationally Notifiable Disease Surveillance System (NNDSS): Timely Case Reporting
NNDSS is a collaboration between CDC and jurisdictions across the country that supports sharing and monitoring public health information for a set of diseases and conditions of national interest. NNDSS has roots extending to a system established in 1893 by Congress for jurisdictions to report cases of disease to the Surgeon General. Over time the system expanded, with responsibility for overseeing the system transferred to CDC in 1961. Local and state public health departments have the authority and responsibility to track cases of disease, typically through reporting from health care providers, laboratories, and other sources. In turn, jurisdictions then may provide case information to CDC through NNDSS. Key characteristics of NNDSS include:
A set of approximately 120 diseases and conditions that are designated by CDC as “nationally notifiable,” meaning the agency requests state and local health departments report to CDC when new cases of any of these conditions are identified. Measles is a nationally notifiable disease, and has been since 1912. Importantly, CDC cannot require jurisdictions to report case information, but all do, especially for high consequence infectious diseases such as measles. CDC itself says “since continuous endemic measles transmission has been eliminated, measles is an immediately notifiable disease.”
For each NNDSS disease or condition there is a pre-established definition that jurisdictions can consult to help determine if a notifiable case has occurred. These case definitions assure a level of standardization across jurisdictions. The definitions for nationally notifiable diseases are developed in collaboration with the Council of State and Territorial Epidemiologists (CSTE) and intermittently updated and refined. The current NNDSS case definition for measles dates to 2013.
Jurisdictions determine the extent of detail provided in their reports. Information shared through NNDSS is “de-identified” (i.e. with personally identifying information removed), but jurisdictions may include demographic, clinical, and epidemiologic characteristics and the course of clinical illness (including whether death occurred) in their case reports.
NNDSS reports can preliminarily indicate the cause of death in a particular case, but are not expected or designed to be a final determination. For this reason, Pennsylvania has reported the four deaths as being “measles-associated” rather than presenting a final determination of measles as the cause of death. The NNDSS definition for measles does not include specific guidance for when and how to report a death as being caused by measles infection, though CDC reports it is working with CSTE to update the definition “to promote consistent classification and reporting of measles deaths across jurisdictions.”
A relative strength of NNDSS is the ability for rapid communication of case-level epidemiologic information between jurisdictions and the CDC, which can allow for near real-time tracking of outbreaks and disease trends. A limitation is that rapidly reported information may only be preliminary in nature, and case reports could be incomplete or lacking in detail.
Table 1
Characteristics of the CDC’s Nationally Notifiable Disease Surveillance System (NNDSS) Case Data and NCHS’ National Vital Statistics System (NVSS) Mortality Data
Characteristic
CDC – NNDSS Case Data
NCHS – NVSS Mortality Data
Primary Purpose
Timely tracking of cases of important diseases and conditions occurring nationwide
Comprehensive tracking of mortality statistics, including cause of death
Basic Unit of Reporting
Cases (such as cases of measles infection); can include associated clinical outcomes such as death
Deaths
Primary Data Source(s)
Reports submitted by state/local departments of health
Death certificate data from state/local vital statistics offices
Timing/speed
Near real-time for high consequence infectious diseases such as measles
A lag of 3 months up to a year between deaths and release of data
Approach to Death Attribution
Potential provisional attribution of death related to a case (e.g. “measles associated” death) as determined by a jurisdictional health department’s analysis of clinical, epidemiological, laboratory, and other criteria
Cause of death must be determined by a licensed provider such as a physician/coroner, and attribution can incorporate multiple factors as contributing causes to death
Key Strengths Related to Reporting Deaths
Timely data collection and analysis supports rapid response and ongoing tracking of public health threats
Comprehensiveness and completeness of mortality data and causes of death
Key Limitations and Challenges Related Reporting Deaths
Reported death information is preliminary in nature and may require further investigation/confirmation; reporting is voluntary and may not be complete
Time lag between deaths and data availability
Sources: CDC, NCHS, and KFF Analysis.
National Vital Statistics System (NVSS): Comprehensive Cause of Death Reporting
NVSS is the federal government’s primary mechanism for tracking mortality (and other vital statistics) data. The NVSS has roots going back to 1902, when Congress created a permanent Census Bureau and authorized the government to obtain copies of state vital records. By 1933, all states were required to record births and deaths and provide data to the Census Bureau. The NCHS was created in 1960, with responsibility for federal vital statistics transferred there. The responsibility and legal authority for documenting births, deaths, and other vital statistics resides at the state and local level, but by statute NCHS has authority to collect and review these data – each state has a contract with NCHS that allows the federal government access to this information to produce national vital statistics. Key characteristics of NVSS include:
Housing the most complete set of data on deaths and births in the U.S. Death certificate information captured through NVSS is the most comprehensive source for mortality information nationally.
Death certificate information captured through NVSS is considered the benchmark for cause of death data. When completing a death certificate, a provider must include the best and final judgement on the proximate cause(s) of death as well as potential other factors that may have contributed to the death. Information from an autopsy, or laboratory and other test results may be included. Demographic details are also reported through the system such as age, sex, race/ethnicity, and education.
Nuances regarding a possible chain of events leading to a death and potentially multiple contributing factors can introduce complexity in cause of death determinations. Regarding the Pennsylvania cases, there has been some debate about measles being a primary cause of the deaths reported by the PA DOH, especially in relation to one of the initial reported deaths – a newborn infant that died from a lacerated spleen but was also positive for measles.
State/local vital records offices are responsible for inspecting death certificates for timeliness, completeness, and accuracy of information, processing, and storing the records. Data files derived from these state/local records are then transmitted to NCHS.
NCHS reviews and processes vital statistics data and codes mortality statistics according to the current revision of the International Classification of Diseases (presently ICD-10, which the U.S. began to use in 1999). ICD-10 provides definitions and rules for selecting the underlying cause of death when generating vital statistics through NVSS. Typically, NVSS will release “provisional” cause of death data with a 3 to 9 month lag (depending on the cause of death), though full provisional data may take up to one a year to be released. Final cause of death data is made available after about two years. For example, the most recent NVSS provisional cause of death data are for 2025 while the most recent final cause of death data are from 2024. In special circumstances, provisional death data can become available even earlier – for example, during the COVID-19 pandemic NVSS provided updated COVID-19 related death statistics on a weekly basis.
A relative strength of the NVSS is its completeness and the comprehensiveness of its cause of death information. A relative weakness of the NVSS is the time lag between when deaths occur and the availability of cause of death data.
Originally published on July 29, 2026, this brief has been updated to reflect newer guidance on the medical frailty exclusion from the Centers for Medicare & Medicaid Services (CMS).
The 2025 reconciliation law requires 44 states to condition Medicaid eligibility for adults in the Affordable Care Act (ACA) Medicaid expansion group and enrollees in certain waiver programs, on meeting work requirements starting January 1, 2027, or sooner at state option. While the law specifies mandatory exclusions, including for individuals who are “medically frail,” the approach to determining medical frailty specified in the June 2026 interim final rule could make it difficult for some people to qualify for this exclusion. Medicaid expansion provides coverage to many adults with significant health care needs, including some with disabilities who are applying for the Supplemental Security Income Program (SSI). This coverage could be at risk for some because of the planned approach to defining medical frailty.
SSI is a means-tested federal program administered by the Social Security Administration (SSA) that pays monthly cash assistance to people with limited resources who are unable to work because of a disability and generally qualifies people to receive health coverage through Medicaid. Once approved for SSI, Medicaid enrollees would not be subject to work requirements, but the application for SSI can be a lengthy and complicated process, spanning months, if not years, during which time applicants may be at risk of uninsurance because they are unable to work. Medicaid can fill coverage gaps during the SSI application period, particularly in states that have adopted the Medicaid expansion.
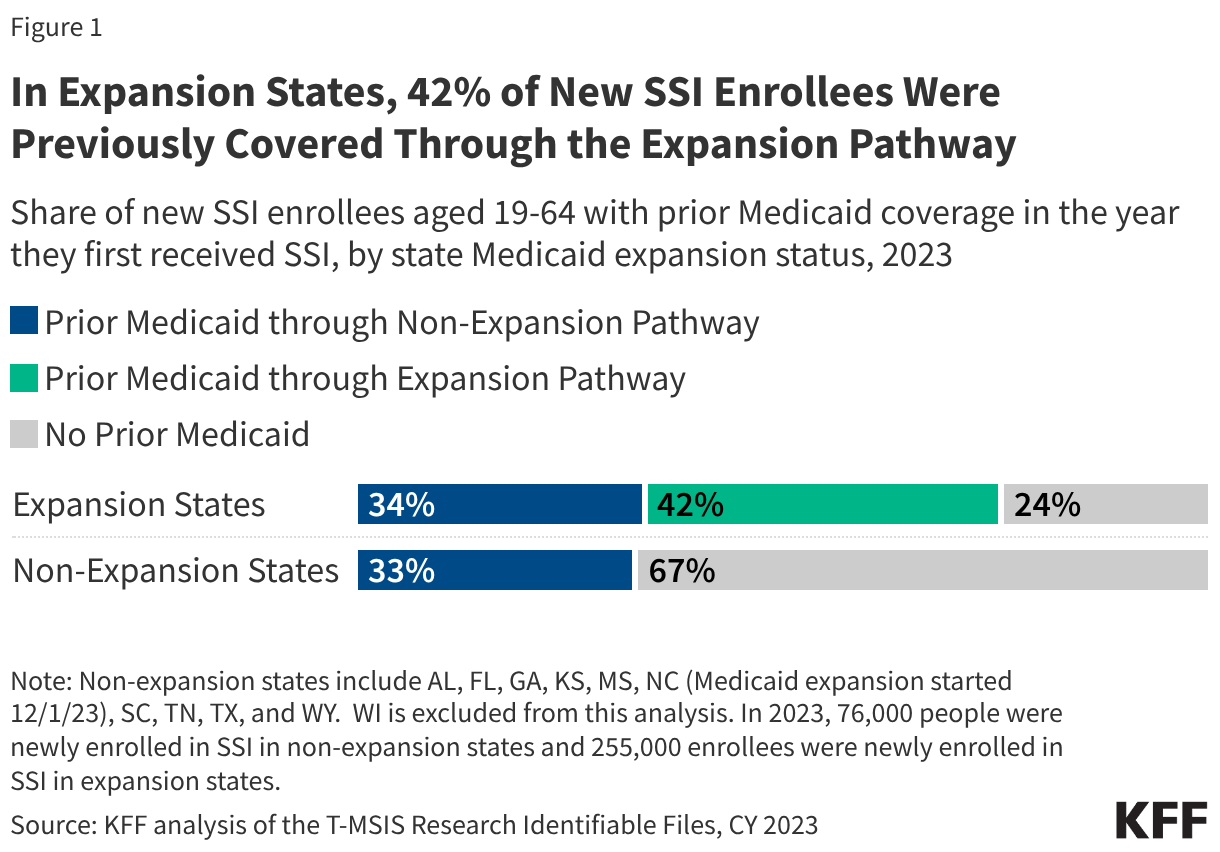
This issue brief finds that the percent of new SSI enrollees ages 19 through 64 with Medicaid prior to SSI entitlement is twice as high in ACA expansion states as it is in non-expansion states, and in 2023, over 100,000 new SSI enrollees had ACA Medicaid coverage prior to their SSI entitlement. It also describes the lengthy SSA process for determining SSI eligibility, particularly assessing ability to work, and how the current approach to determining medical frailty could cause some SSI applicants to undergo concurrent assessments of their ability to work using different processes and criteria. The new documentation requirements and processes could cause some people with disabilities to lose Medicaid coverage or be denied Medicaid enrollment while they are waiting on their SSI determination. (For analysis on the implications of Medicaid work requirements for people applying for the Social Security Disability Insurance (SSDI) program or waiting for Medicare coverage, see What Could Medicaid Work Requirements Mean for People with Disabilities Waiting for Medicare Coverage?)
How does Medicaid provide coverage for people during the SSI application process?
Medicaid provides coverage for many people with disabilities, including those who are applying for SSI.One in five Medicaid enrollees have a disability, including 43% of adults ages 50-64, but only one-third of these individuals receive SSI income, generally qualifying for Medicaid for that reason. The remaining people with disabilities are covered through different Medicaid eligibility pathways, including the ACA Medicaid expansion. Because of the lengthy process for obtaining an SSI determination and the fact that people who are applying for SSI are unable to work, many people applying for SSI rely on Medicaid to avoid going uninsured.
In 2023, 223,000 SSI applicants ages 19 through 64 had Medicaid while they were waiting for an SSI determination, including over 106,000 with coverage through the ACA expansion. KFF analyzed detailed Medicaid administrative data to identify people who were ages 19 through 64 and became eligible for Medicaid because of SSI during the calendar year 2023 and whether those enrollees had Medicaid coverage in the months prior to their SSI-based eligibility (see Methods). Among the 337,000 people who started SSI during the calendar year, over 200,000 had prior Medicaid coverage through a different eligibility pathway, with roughly half receiving that coverage through the ACA expansion.
In ACA expansion states, 76% of new SSI enrollees ages 19 through 64 had Medicaid coverage through a different eligibility pathway prior to their disability determination (including 42% who were covered through the Medicaid expansion) compared with only 33% in non-expansion states (Figure 1). In both expansion and non-expansion states, roughly 1 in 3 new SSI enrollees ages 19 through 64 were enrolled in non-ACA Medicaid coverage (such as coverage for parents and caretakers) prior to becoming eligible for SSI. However, in expansion states, an additional 42% of new SSI enrollees were enrolled in Medicaid through the expansion, covering over 100,000 people in 2023. New SSI enrollees who were not covered by Medicaid prior to their SSI approval were likely uninsured because of their low income and inability to work.
In Expansion States, 42% of New SSI Enrollees Were Previously Covered Through the Expansion Pathway
Share of new SSI enrollees aged 19-64 with prior Medicaid coverage in the year they first received SSI, by state Medicaid expansion status, 2023
Non-expansion states include AL, FL, GA, KS, MS, NC (Medicaid expansion started 12/1/23), SC, TN, TX, and WY. WI is excluded from this analysis. In 2023, 76,000 people were newly enrolled in SSI in non-expansion states and 255,000 enrollees were newly enrolled in SSI in expansion states.
KFF analysis of the T-MSIS Research Identifiable Files, CY 2023
How do people demonstrate eligibility for SSI?
To be eligible for SSI, people must have limited income (defined as no more than $2,073 per month in 2026), limited resources (defined as no more than $2,000 for an individual or $3,000 for a couple), and a disability that affects their ability to work for at least a year or result in death or be age 65 and older.
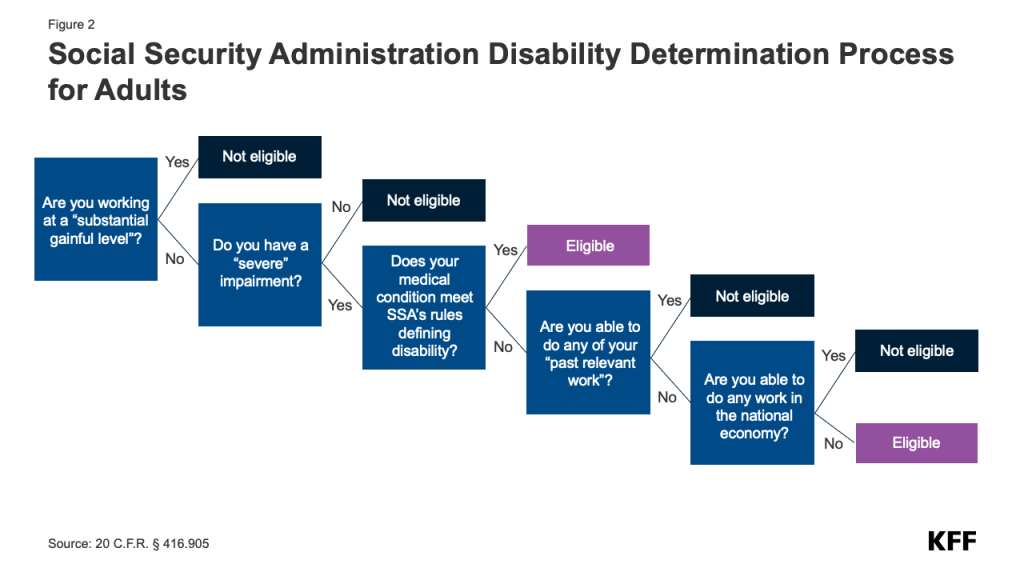
For applicants under age 65, demonstrating a disability is often the most complicated part of the SSI application process, involving a lengthy five-step process that starts by proving one is not gainfully employed (Figure 2). The federal government establishes verification processes that all states must use to determine applicants’ disability status, and funds state Disability Determination Services (DDS) offices to carry out these processes. The same processes are used for SSI and for Social Security Disability Insurance. Illustrating the high costs of this lengthy process, the Social Security Administration provided states with $2.6 billion in Fiscal Year (FY) 2025 to run the DDS offices. The first step requires people to demonstrate that their current earnings are below the threshold of “substantial gainful activity” (SGA, $1,690 per month in 2026).
The second step assesses whether applicants have a severe impairment, where impairment is defined based on which body system is affected. For adults, impairments are classified into the following categories with associated medical criteria: musculoskeletal disorders, special senses and speech, respiratory disorders, cardiovascular system, digestive disorders, genitourinary disorders, hematological disorders, skin disorders, endocrine disorders, congenital disorders that affect multiple body systems, neurological disorders, mental disorders, cancer, and immune system disorders.
The third step assesses whether the impairment qualifies as a disability that wouldn’t require further demonstration of an inability to work using established criteria for disabilities. Some impairments allow applicants to qualify for SSI without further demonstrating an inability to work, including blindness and several hundred specific disorders or conditions included in the “compassionate allowance program,” which quickly identifies diseases and other conditions that meet SSA’s standards for disability benefits. Examples of such conditions include Amyotrophic Lateral Sclerosis (ALS), certain cancers, and Duchenne Muscular Dystrophy. SSA reports that between 2008 and 2025, the agency approved more than 1 million people (for SSI and Social Security Disability Insurance combined) through the compassionate allowance program.
The final two steps respectively assess peoples’ ability to engage in “past relevant work” or any job in the national economy that is feasible considering the applicant’s residual functional capacity, age, education, and work experience. The SSA makes this assessment based on information provided in Form 3368 which requires people to provide personal information including their English language proficiency, current work activity, job history over the last 15 years, the claimed disability onset date, list of medical conditions, prescription list, and medical treatment history. Medical records from providers can be submitted with the application. Along with this form, the SSA will request any missing medical records and may request that the person have a consultative medical examination by an SSA medical consult. SSA also compares information about people’s jobs from the past 5 years (such as job title and pay; tasks performed; tools, machinery, and equipment used; knowledge, skills, and ability required; physical demands; and environmental conditions) with tables of rules about the requirements for jobs in the national economy.
Assessing ability to engage in any job requires information about all jobs in the economy, which can be difficult to implement in practice, and SSA is currently relying on outdated job information. SSA’s current jobs listing comes from the Department of Labor’s Dictionary of Occupational Titles which was last updated in 1991 and is not currently used by the Department of Labor. Since FY 2021, SSA has partnered with the Department of Labor to develop a survey that will be the main source of updated occupational information, but that new system has not yet been implemented. Congressional Research Services reports that between FYs 2012 and 2024, SSA spent $300 million on this project.
The application for disability benefits can be a lengthy and complicated process, spanning months, if not years, meaning hundreds of thousands of people are currently waiting for determinations. As of May 2026, the initial processing time for all disability applications was 184 days—over 6 months—and roughly 862,000 people were waiting for their initial determinations. (This number includes applications for SSI and applications for Social Security Disability Insurance, a related program that uses the same disability determination process.) Many people receive initially unfavorable decisions and choose to appeal, which can considerably lengthen the process. Having a lawyer increases the likelihood of being approved at the initial stage and, on average, can reduce the time it takes to reach a final decision by nearly one year.
How might work requirements affect Medicaid coverage for people during the SSI application process?
Starting in January 2027, individuals applying for or enrolled in coverage through the ACA expansion and in certain waiver programs will be required to work or engage in qualifying activities, such as community service, for 80 or more hours per month, attend school half-time, unless they qualify for an exemption or exclusion from the requirements. SSI applicants enrolled in the ACA Medicaid expansion will be subject to these new requirements. SSI applicants may face challenges proving their eligibility for the medical frailty exclusion while they wait for an eligibility determination from SSA.
People applying for SSI are generally unable to work, but current rules could make it challenging for them to qualify for a medical frailty exclusion. Because individuals must have earnings below the SGA level to be eligible for SSI, they are unlikely to be able to work 80 or more hours in a month and are unlikely to be able to meet the Medicaid community engagement requirements through education or volunteering. Instead, to obtain or retain Medicaid, individuals applying for SSI who are subject to the work requirements will need to qualify for an exclusion from the requirements, most likely through the medical frailty exclusion. The interim final rule implementing Medicaid work requirements issued on June 1, 2026, adopts a restrictive definition of medical frailty that requires individuals to have a physical or mental health condition that impairs their ability to meet community engagement requirements. This two-part test for medical frailty will require navigating a verification process that may lead to some people who would qualify for the exclusion losing coverage because they cannot provide the required documentation.
Different requirements for Medicaid eligibility determinations mean SSI applicants covered through the Medicaid expansion could face two concurrent assessments of their ability to work: one for SSI and one for Medicaid. Medicaid eligibility determinations of whether an individual meets the medical frailty exclusion will need to be done on a faster timeline than SSI determinations. States are required to process Medicaid applications for individuals who qualify based on income within 45 days, and starting January 1, 2027, they must conduct renewals for individuals enrolled through the Medicaid expansion every six months instead of annually. That makes it likely that many SSI applicants will not have a disability determination before they have an assessment of their ability to work to meet the medical frailty exclusion from Medicaid work requirements. These new requirements could place additional administrative burdens on individuals who are experiencing significant physical or mental health challenges and could cause people to lose health insurance while they wait for an SSA disability determination.
New guidance from the Centers for Medicare & Medicaid Services (CMS) may help to mitigate but will not eliminate the risk that SSI applicants may lose Medicaid coverage. The interim final rule requires states to verify medical frailty on an ex parte basis where possible, using reliable information available to the state without requiring the individual to submit additional information. CMS recently released a slide deck that outlined a tiered medical frailty framework that states may follow using data from claims and other sources to identify people who meet the medical frailty exclusion. While states are not required to adopt this approach, the tiered medical frailty framework would enable states to identify individuals as medically frail using claims data alone (tier 1), using claims data in combination with encounter or other data (tier 2), or, in cases where states have no or insufficient data on file, using an individualized manual process that requires additional documentation (tier 3). As they develop processes for verifying medical frailty, states will rely more heavily on provider determinations or other documentation and self-attestation, to the extent permitted by the rule, for individuals who cannot be automatically verified. Self-attestation will be permitted in 2027, but starting in 2028, it will only be permitted once per continuous enrollment period, meaning states will need to collect documentation at renewal for medically frail individuals. Even with use of data to verify medical frailty, the documentation requirements could cause some people with disabilities to lose Medicaid coverage or be denied Medicaid while they are waiting on their SSI determination.
This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.
Methods
Data: Data are from the 2023 Transformed Medicaid Statistical Information System (T-MSIS) Analytic Files (TAF) Research Identifiable Files (RIF) files.
State inclusion criteria: National estimates include enrollees living in 49 states and DC and exclude residents in the U.S. territories. Non-expansion states include AL, FL, GA, KS, MS, NC (Medicaid expansion started 12/1/23), SC, TN, TX, and WY. WI is excluded from this analysis because it has an 1115 waiver that offers coverage similar to the ACA expansion. The pre-SSI Medicaid coverage rates look much more similar to those of an ACA expansion state, but the T-MSIS data do not clearly identify people enrolled in the 1115 coverage.
Identifying new SSI enrollees using Medicaid administrative data: Enrollees are classified as new SSI enrollees if their latest eligibility group in the year is SSI (having ELGBLTY_GRP_CD_LTST with value of 11-22, 37, 38, 40, or 41) but in January, they are either not enrolled in Medicaid or they are enrolled through some other pathway (ELGBLTY_GRP_CD_01 not having value of 11-22, 37, 38, 40, or 41). The analysis is limited to enrollees ages 19 through 64 who are in Medicaid only (and not CHIP) during the year.
Assessing prior Medicaid coverage in the year for new SSI enrollees: Monthly eligibility group codes (ELGBLTY_GRP_CD_01-ELGBLTY_GRP_CD_12) are used to determine the first month of SSI enrollment (first monthly eligibility group code with value of 11-22, 37, 38, 40, or 41). Then, all monthly eligibility group codes prior to the first month of SSI enrollment are used to assess prior Medicaid enrollment during the year as follows:
Prior Medicaid coverage through the expansion pathway: having at least one monthly eligibility group code indicating enrollment through the ACA expansion group (value of 72, 73, 74, or 75) before the first month of SSI enrollment.
Prior Medicaid coverage through non-expansion pathway: having at least one non-missing monthly eligibility group code and no monthly eligibility group codes indicating enrollment through the ACA expansion group (value of 72, 73, 74, or 75) before the first month of SSI enrollment.
No prior Medicaid coverage: eligibility group codes for all months before the first month of SSI enrollment are missing.
The Social Security Disability Insurance (SSDI) program provides monthly benefits to people who are unable to work on account of a long-term disability. SSDI beneficiaries qualify for Medicare, but in most cases, must wait 24 months between their entitlement to receive SSDI benefits and Medicare eligibility, referred to as the “Medicare waiting period.” The SSDI application process can take months, if not years. During this time and the subsequent Medicare waiting period, some people may be at risk of going without health insurance because they do not have Medicare but are unable to work due to a disability.
The Affordable Care Act (ACA) Medicaid expansion provides coverage for some SSDI applicants and SSDI beneficiaries waiting to become eligible for Medicare. The 2025 reconciliation law requires 44 states to condition Medicaid eligibility for adults in the ACA Medicaid expansion group and enrollees in certain waiver programs on meeting work requirements starting January 1, 2027, or sooner at state option. While the law specifies mandatory exclusions, including for individuals who are “medically frail,” the approach to determining medical frailty specified in the June 2026 interim final rule could make it difficult for some people, including SSDI applicants and SSDI beneficiaries waiting for Medicare, to qualify for this exclusion.
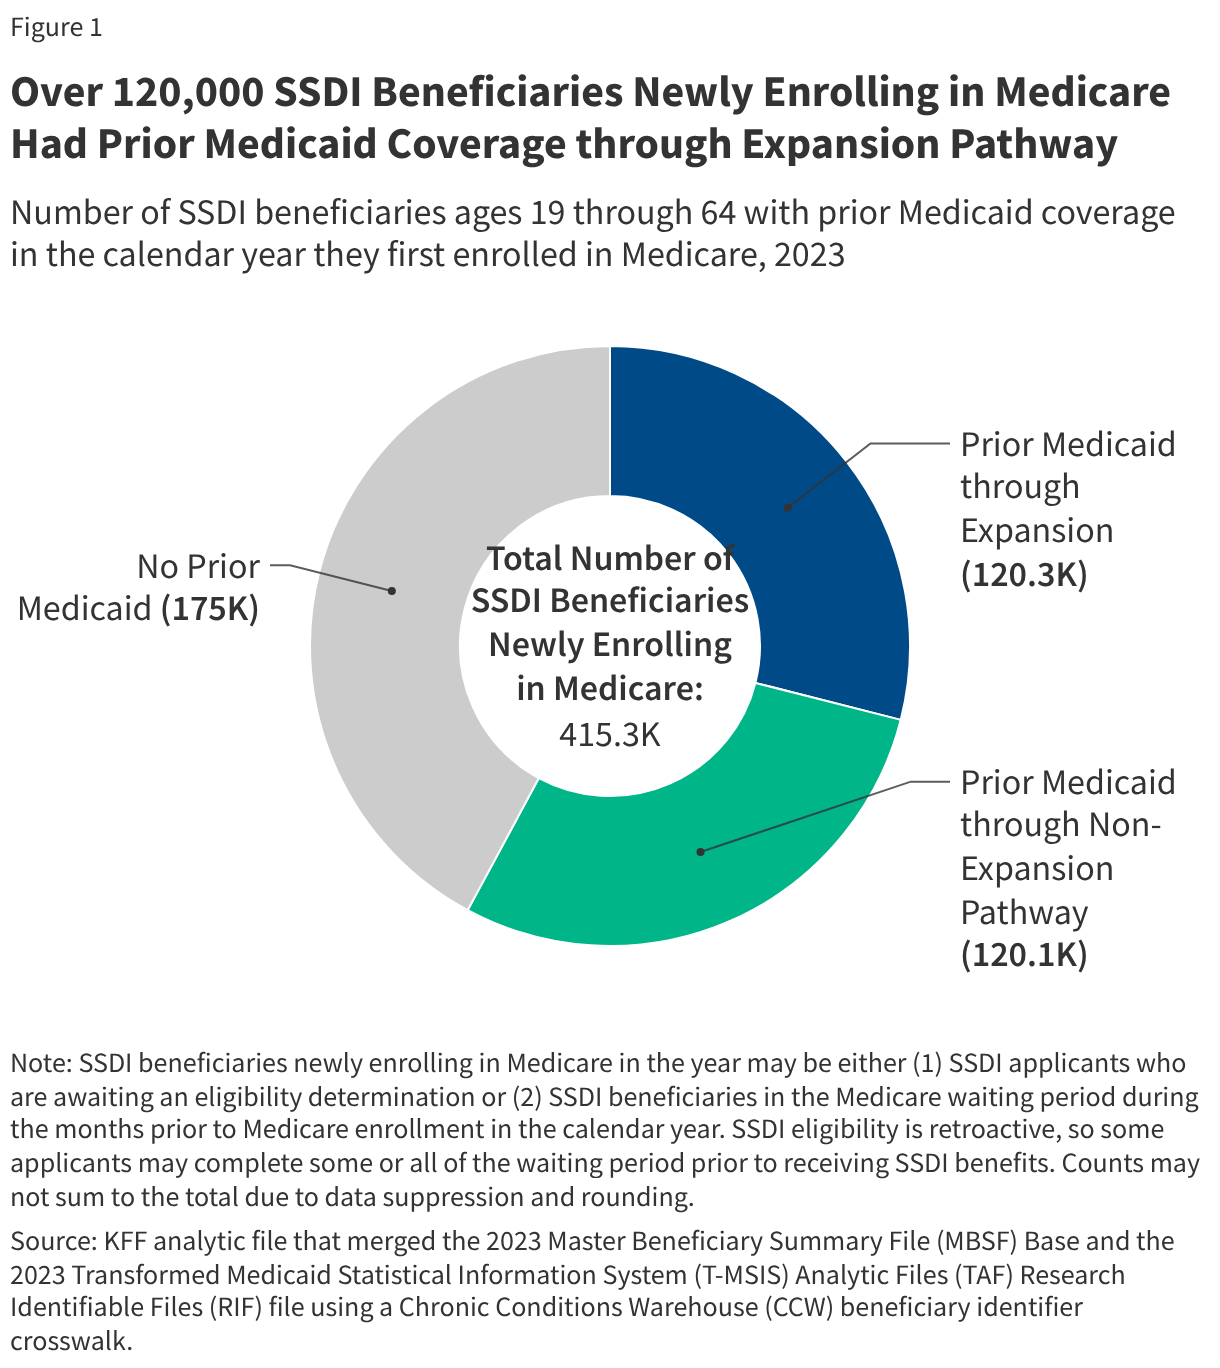
This issue brief explains how Medicaid provides coverage to some SSDI applicants and SSDI beneficiaries waiting for Medicare. KFF used linked Medicare and Medicaid administrative data from 2023 to analyze prior Medicaid coverage for SSDI beneficiaries ages 19 through 64 newly enrolling in Medicare (see Methods). The analysis finds that Medicaid through the expansion pathway covered over 1 in 4 SSDI applicants and beneficiaries waiting to become eligible for Medicare (120,300 people out of a total 415,300 in 2023). In future years, people applying for and new to SSDI may experience difficulties maintaining Medicaid prior to becoming eligible for Medicare because of the new work requirements. (For analysis on the implications of Medicaid work requirements for people applying for the Supplemental Security Income (SSI) program, see What Could Medicaid Work Requirements Mean for SSI Applicants?)
How does Medicaid provide coverage for people who are applying for and receiving SSDI?
Medicaid provides coverage for many people with disabilities, including some who are applying for SSDI or are receiving SSDI benefits but are not yet eligible for Medicare.One in five Medicaid enrollees have a disability, including 43% of enrollees ages 50-64. One-third of those people receive Supplemental Security Income (SSI). SSI is a separate federal program that provides monthly income to people who are unable to work because of a disability and who have income and financial resources below federal limits. The remaining people with disabilities are covered through different Medicaid eligibility pathways, including the ACA Medicaid expansion. During the SSDI application process, which can take months, if not years, or the Medicare waiting period, people may rely on Medicaid for their health coverage before becoming eligible for Medicare to avoid going uninsured.
In 2023, 240,300 SSDI beneficiaries enrolled in Medicare after having prior Medicaid coverage, including 120,300 who were enrolled through the Medicaid expansion (Figure 1). KFF used linked Medicare and Medicaid data to examine how many SSDI beneficiaries ages 19 through 64 newly enrolling in Medicare had any prior Medicaid coverage in 2023 (see Methods). Among the 415,300 SSDI beneficiaries newly enrolling in Medicare in 2023, 240,300 (58%) had prior Medicaid coverage through any eligibility pathway, with 120,300 of those having coverage through the expansion pathway specifically.
Over 120,000 SSDI Beneficiaries Newly Enrolling in Medicare Had Prior Medicaid Coverage through Expansion Pathway
Number of SSDI beneficiaries ages 19 through 64 with prior Medicaid coverage in the calendar year they first enrolled in Medicare, 2023
SSDI beneficiaries newly enrolling in Medicare in the year may be either (1) SSDI applicants who are awaiting an eligibility determination or (2) SSDI beneficiaries in the Medicare waiting period during the months prior to Medicare enrollment in the calendar year. SSDI eligibility is retroactive, so some applicants may complete some or all of the waiting period prior to receiving SSDI benefits. Counts may not sum to the total due to data suppression and rounding.
KFF analytic file that merged the 2023 Master Beneficiary Summary File (MBSF) Base and the 2023 Transformed Medicaid Statistical Information System (T-MSIS) Analytic Files (TAF) Research Identifiable Files (RIF) file using a Chronic Conditions Warehouse (CCW) beneficiary identifier crosswalk.
How do people become eligible for Medicare through SSDI?
People must first demonstrate eligibility for SSDI, a process that can take months and often years. To qualify for SSDI, enrollees must have a sufficient work history and a disability that affects their ability to work and is expected to last for at least a year or result in death. A sufficient work history varies by age but generally requires 10 years of employment, at least five of which were within the past decade. Some individuals with a disability can qualify based on a relative’s work history.
The SSDI application process can be a lengthy and complicated process, spanning months, and in some cases years. Demonstrating a disability is often the most complicated part of the SSDI application process. The federal government establishes verification processes that all states must use and utilizes the same five-step process to determine applicants’ disability status for both SSDI and SSI. (For a more detailed description of this process, see What Could Medicaid Work Requirements Mean for SSI Applicants?). As of July 2026, the initial processing time for all disability applications was 186 days, and 885,000 people were waiting for their initial determinations. (This number includes applications for both SSDI and SSI.) Many people receive initially unfavorable decisions and choose to appeal, which can lengthen the process (Figure 2). Because of the process for obtaining an SSDI determination and the fact that people who are applying for SSDI are unable to work, some people applying for SSDI may rely on Medicaid to avoid going uninsured.
SSDI beneficiaries become eligible for Medicare two years after they are entitled to SSDI benefits. Beneficiaries in most cases must wait 5 months for SSDI payments from the disability onset date, followed by a 24-month waiting period between becoming entitled to receive SSDI payments and Medicare eligibility, referred to as the “Medicare waiting period.” Because of the length of the SSDI application process and the fact that SSDI eligibility is retroactive, applicants may complete some or all of the waiting period prior to receiving SSDI benefits.
While many SSDI beneficiaries waiting for Medicare rely on Medicaid to avoid going uninsured, others face health insurance coverage gaps during the Medicare waiting period. SSDI beneficiaries in the Medicare waiting period tend to have low incomes, poor health, and fragile ties to the workforce. SSDI beneficiaries who are uninsured during the Medicare waiting period are more likely to report being in poor health, having more difficulties in activities of daily living, and having higher out-of-pocket medical expenditures than those with insurance. Research predating the ACA Medicaid expansion found that about a quarter of SSDI beneficiaries in the Medicare waiting period were uninsured.
How might Medicaid work requirements affect Medicaid coverage for SSDI beneficiaries before they become eligible for Medicare?
The new work requirements may make it difficult for SSDI applicants and SSDI beneficiaries waiting for Medicare to maintain Medicaid coverage before becoming eligible for Medicare. Starting in January 2027, individuals applying for or enrolled in Medicaid coverage through the ACA expansion and in certain waiver programs will be required to work or engage in qualifying activities, such as community service, for 80 or more hours per month, attend school half-time, or qualify for an exemption or exclusion from the requirements. SSDI applicants and SSDI beneficiaries waiting for Medicare enrolled in the ACA Medicaid expansion will be subject to these new requirements. SSDI applicants and SSDI beneficiaries waiting for Medicare may face challenges proving they meet the requirements or that they are eligible for exemptions or exclusions, although the issues each group will encounter may differ because they are in different stages of the SSDI determination process.
People applying for SSDI are generally unable to work, but current rules could make it challenging for them to qualify for a medical frailty exclusion. Because individuals must have earnings below the level of “substantial gainful activity” (SGA, $1,690 per month in 2026) to be eligible for SSDI, they are unlikely to be able to work 80 or more hours in a month. Additionally, most people with new impairments significant enough to qualify for SSDI will likely also face challenges meeting the Medicaid work requirements through education or volunteering. Instead, to obtain or retain Medicaid, individuals applying for SSDI who are subject to the work requirements will need to qualify for an exclusion from the requirements, most likely through the medical frailty exclusion. The interim final rule implementing Medicaid work requirements issued on June 1, 2026 adopts a definition of medical frailty that requires individuals to have a physical or mental health condition and that the condition must impair their ability to meet work requirements. This two-part test for medical frailty will require navigating a verification process that may lead to some people who would qualify for the exclusion losing coverage because they cannot provide the required documentation.
New guidance from the Centers for Medicare & Medicaid Services (CMS) may help to mitigate but will not eliminate the risk that SSDI applicants may lose Medicaid coverage. The interim final rule requires states to verify medical frailty on an ex parte basis where possible, using reliable information available to the state without requiring the individual to submit additional information. CMS recently released a slide deck that outlined a tiered medical frailty framework that states may follow using data from claims and other sources to identify people who meet the medical frailty exclusion. While states are not required to adopt this approach, the tiered medical frailty framework would enable states to identify individuals as medically frail using claims data alone (tier 1), using claims data in combination with encounter or other data (tier 2), or, in cases where states have no or insufficient data on file, using an individualized manual process that requires additional documentation (tier 3). As they develop processes for verifying medical frailty, states will rely more heavily on provider determinations or other documentation and self-attestation, to the extent permitted by the rule, for individuals who cannot be automatically verified. Self-attestation will be permitted in 2027, but starting in 2028, it will only be permitted once per continuous enrollment period, meaning states will need to collect documentation at renewal for medically frail individuals. Even with increased use of data to verify medical frailty, the documentation requirements could cause some people with disabilities to lose Medicaid coverage or be denied Medicaid while they are waiting on their SSDI determination.
SSDI beneficiaries waiting for Medicare should qualify for the medical frailty exclusion from work requirements but may still be at risk of losing Medicaid coverage depending on how states implement new systems. The medical frailty exclusion includes people who are blind or disabled according to the Social Security Administration (SSA) definition of disability. SSDI beneficiaries waiting for Medicare have already been determined to meet the SSA definition of disability and have a disability that limits their ability to work, meaning that they would likely qualify for the medical frailty exclusion. However, depending on state processes, SSDI beneficiaries waiting for Medicare may not be automatically identified as medically frail and may be required to show documentation of their SSDI determination.
This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.
Appendix: Timelines for Disability Determinations and Medicare Coverage
Disability Determination Process for Applicants Who Appeal
Figure 2
Disability Determinations Can be a Multi-Step and Lengthy Process, Potentially Spanning Years
Note: The number of people who reached each stage of the disability determination and appeals decisions issued in FY 2025, regardless of the year in which the initial claim was filed and whether the claimant ever received benefits. Average processing times for initial disability claim, reconsideration, administrative judge hearing are the average processing times reported as of July 2026. The Social Security Administration (SSA) does not report average processing times for appeals council and federal court decision stages. The most recent average processing time for appeals council reported was 364 days as of 2016.
Timeline from Disability Onset to Medicare Coverage
The over 120,000 SSDI beneficiaries newly enrolling in Medicare with prior Medicaid coverage through Medicaid expansion may either be SSDI applicants or SSDI beneficiaries waiting for Medicare in the months in the calendar year prior to Medicare enrollment. Because SSDI eligibility is retroactive, some SSDI applicants may complete some or all of the Medicare waiting period prior to receiving SSDI benefits (Figure 3). This means that some SSDI applicants may become eligible for Medicare as soon as they are determined to qualify for SSDI. Other SSDI beneficiaries newly enrolling in Medicare receive SSDI payments and are in the Medicare waiting period in the months immediately preceding enrollment in Medicare (Figure 4). Using the data available, it is not possible to determine the exact number of SSDI beneficiaries newly enrolling in Medicare who are SSDI applicants or SSDI beneficiaries waiting for Medicare in the months prior to Medicare enrollment in the year.
Figure 3
Medicare Waiting Period Completed During SSDI Application Process
Note: Initial determination, reconsideration, and administrative law judge hearing wait times are based on average wait times as reported in SSA performance data.
Source: 42 U.S.C. § 426(b), SSA performance data (accessed September 2026)
Figure 4
Medicare Waiting Period Completed After SSDI Cash Benefits Begin
Note: Initial determination wait time is based on average wait times as reported in SSA performance data.
Source: 42 U.S.C. § 426(b), SSA performance data (accessed September 2026)
Methods
Data: Data are from KFF analytic files that merge the Centers for Medicare & Medicaid Services (CMS) Chronic Conditions Data Warehouse (CCW) 2023 research-identifiable Master Beneficiary Summary File (MBSF) Base and the 2023 Transformed Medicaid Statistical Information System (T-MSIS) Analytic Files (TAF) Research Identifiable Files (RIF) using a CCW beneficiary identifier crosswalk.
State inclusion criteria: National estimates include enrollees living in 50 states and DC and exclude residents in the U.S. territories.
Identifying SSDI beneficiaries newly enrolling in Medicare using administrative data: Enrollees are classified as SSDI enrollees newly enrolling in Medicare if they have a coverage start date (COVSTART) February 2023 through December 2023, did not have Medicare Part A or Part B in January 2023 (MDCR_ENTLMT_BUYIN_IND_01 not having value 1, 2, 3, A, B, or C), have a current entitlement reason equal to disability insurance benefits (DIB) or both DIB and end-stage renal disease (ESRD) (ENTLMT_RSN_CURR with value 1 or 3), and are ages 19 through 64 at the end of the calendar year.
Assessing prior Medicaid coverage in the calendar year for SSDI enrollees newly enrolling in Medicare: The Medicare coverage start date (COVSTART) is used to determine the first month of enrollment in Medicare during the year. Then, all Medicaid monthly eligibility group codes in 2023 (ELGBLTY_GRP_CD_01-ELGBLTY_GRP_CD_12) prior to the first month of Medicare enrollment are used to assess prior Medicaid enrollment during the year using the following hierarchy:
Prior Medicaid coverage through the expansion pathway: having at least one Medicaid monthly eligibility group code indicating enrollment through the ACA expansion group (value of 72, 73, 74, or 75) before the first month of Medicare enrollment.
Prior Medicaid coverage through other pathway: having at least one non-missing Medicaid monthly eligibility group code and no Medicaid monthly eligibility group codes indicating enrollment through the ACA expansion group (value of 72, 73, 74, or 75) before the first month of Medicare enrollment.
No prior Medicaid coverage: Medicaid eligibility group codes for all months before the first month of Medicare enrollment are missing or the Medicare beneficiary did not have any records in T-MSIS.
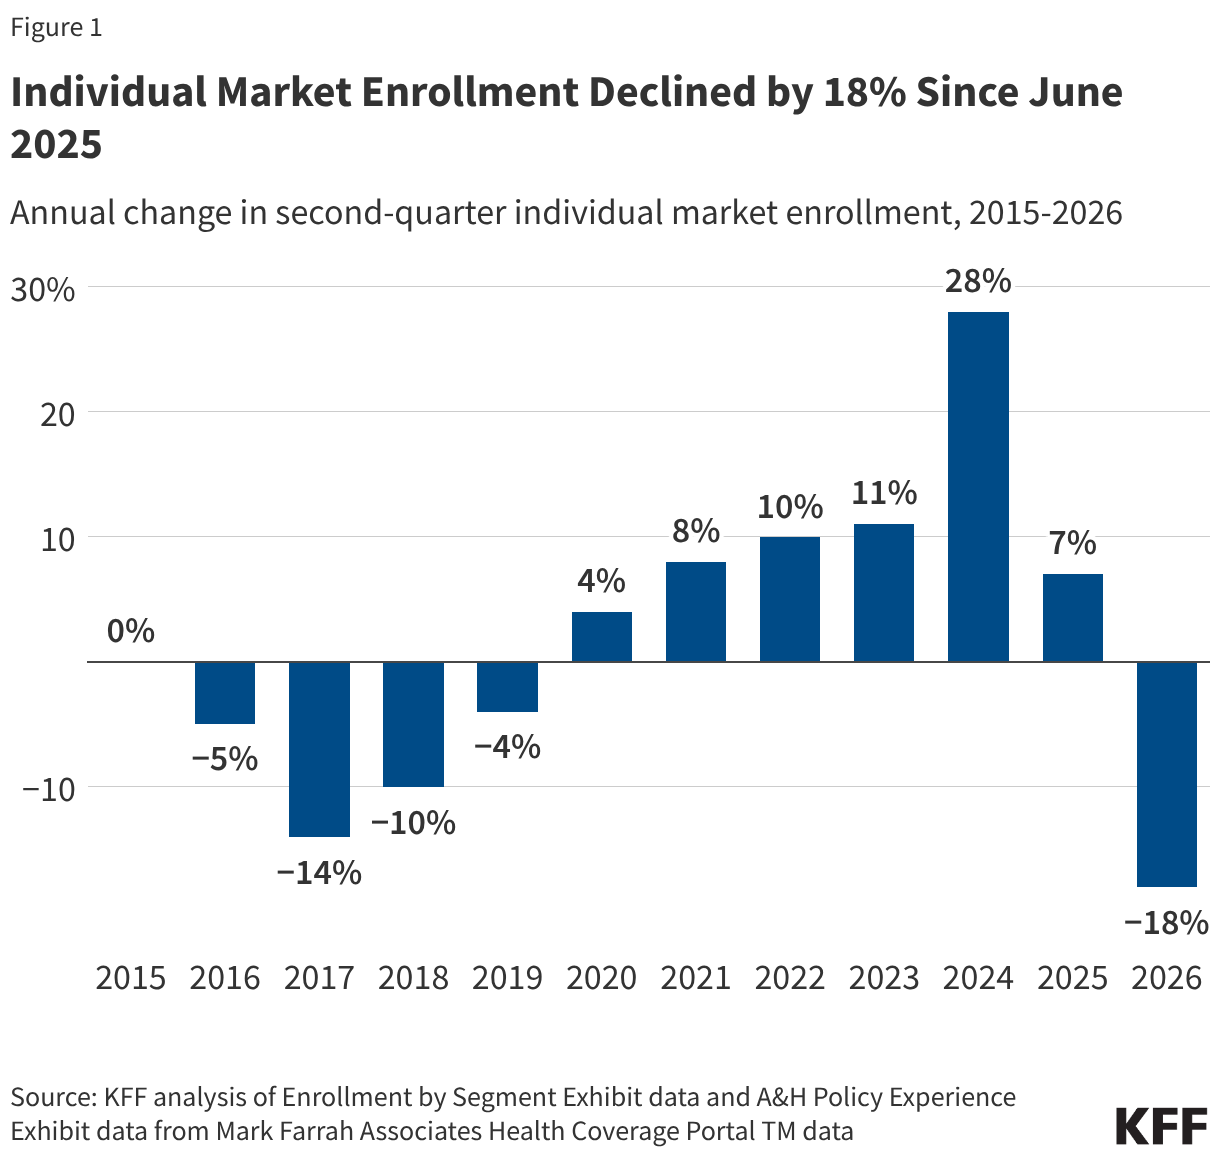
Enrollment in the individual health insurance market fell 18% between June 2025 and June 2026. The individual market is composed primarily of people with Affordable Care Act (ACA) Marketplace coverage as well as some people who buy similar coverage off-exchange. This represents an even steeper drop in enrollment than had previously been reported. Previous data on ACA Marketplace enrollment showed that effectuated enrollment fell 12% from February. Although more current data for the ACA Marketplace population are not yet available, data on the individual market—of which roughly nine in ten people are enrolled through the ACA Marketplaces—suggest enrollment continued to decline, falling 16% as of March and 18% as of June. This decrease includes both on- and off-exchange coverage. In total, we estimate that individual market enrollment has fallen by over 4.6 million people, from 25.2 million in June 2025 to 20.5 million in June 2026.
The enrollment decline coincides with the expiration of the enhanced premium tax credits and other policy changes that are expected to reduce enrollment. As of earlier this year, ACA Marketplace enrollment had fallen in every state except New Mexico, with wide variation in the size of the declines.
Individual Market Enrollment Declined by 18% Since June 2025
Annual change in second-quarter individual market enrollment, 2015-2026
The decline in the individual market enrollment began during the 2026 ACA Marketplace Open Enrollment Period and continued throughout the year. Plan selections, or sign-ups, during the 2026 Open Enrollment Period fell by 1.2 million people from 2025. But plan selections may include people who do not pay their premiums and so never have coverage take effect. Returning subsidized enrollees also have a three-month grace period for nonpayment: those who do not make their premium payments are not dropped from coverage until the grace period elapses. Enrollees that did not make their January premium payment likely were not recorded as terminated until after March 31, with coverage terminated retroactively to the end of January. As a result, February ACA Marketplace effectuated enrollment (measured retrospectively after the grace period elapsed on May 15, 2026) fell by 12%, from 21.8 million to 19.2 million.
Year-over-year March enrollment in the composite individual market showed a continued decrease, falling 16%. By June, enrollment had fallen 18% compared with the same period in 2025. While these numbers include off-exchange enrollment, the bulk of individual market coverage is purchased on-exchange through ACA Marketplaces. Off-exchange coverage, purchased directly from insurers or brokers, does not provide access to financial assistance through premium tax credits but allows insurers additional flexibility in plan design.
These declines approach the Congressional Budget Office (CBO)'s projection of a roughly 25% drop in enrollment through 2026 after the expiration of the enhanced tax credits, and they are consistent with KFF polling of Marketplace enrollees. In KFF’s Follow-Up Survey of ACA Marketplace Enrollees, one in six returning enrollees (17%) said they were not confident they could afford their premiums for all of 2026, which puts them at risk of losing coverage later in the year. Among all 2025 Marketplace enrollees, 22% said they had moved to another source of coverage, and nearly one in ten (9%) said they were now uninsured.
Further enrollment declines may continue this and in upcoming plan years. The second-quarter data provide a mid-year snapshot, and enrollees who fall behind on premiums later in the year may still lose coverage. These June enrollment figures do not account for the drop in enrollment expected from the recent announcement of plan cancelations, which occurred after the end of the second quarter. While enrollment has fallen sharply this year, individual market enrollment is still higher than before the introduction of enhanced premium tax credits by over seven million from June 2019, a change of 53%.
Premiums are also expected to keep rising in 2027. Marketplace insurers have proposed a median premium increase of 15% for 2027, the second consecutive year of double-digit increases. On average, insurers raised premiums by an additional four percentage points in anticipation of further expected enrollment declines and a subsequently sicker risk pool in 2027. As some enrollees encounter higher premiums during the upcoming ACA Open Enrollment Period this fall, enrollment in the individual market may continue to shrink, and more people could become uninsured.
Methods
Data used in this analysis come from the Mark Farrah Associates Health Coverage Portal™. Data from the “Enrollment by Segment” exhibit and the “Accident & Health Policy Experience Exhibit – by Domicile” were used (accessed September 23, 2026). The dataset analyzed in this report includes plans filing the Exhibit of Premiums, Enrollment and Utilization (EPEU)—or the Supplemental Health Care Exhibit (SHCE) when EPEU is not available—with the National Association of Insurance Commissioners (NAIC) and California HMOs regulated by California’s Department of Managed Health Care. Only plans that were categorized as having a “medical” focus were included; “specialty” plans, which is composed of ancillary or supplemental benefit plans, were excluded. Enrollment from the U.S. territories was excluded. Enrollment counts were adjusted to exclude Children’s Health Insurance Program (CHIP) enrollment that may be captured as individual market enrollment for all plans with available data in the Policy Experience exhibit. Enrollment in plans that file SHCE annually at the end of the year (such as life plans that may sell health insurance in the individual market) was also adjusted by the national growth rate from the end of the preceding year to estimate second quarter enrollment. The share of total individual market enrollment derived from SHCE was 2.8% in 2025 and 1.5% in 2026. Among insurers that report quarterly, there was a 5% drop in enrollment between March and June 2026.
Mark Farrah Associates released a report that estimated enrollment fell about 17.2% year-over-year in the second quarter of 2026. The KFF analysis differs by including only plans with a medical focus in the U.S. excluding territories, adjusting for plans that file annually and for CHIP enrollment.
Note: Originally published on Nov. 12, 2025, this resource is updated as needed, most recently on October 12, 2026, to reflect additional developments.
Since assuming office for a second term, President Trump and officials in his administration have instituted numerous policy actions through the Department of Health and Human Services (HHS) affecting public health in the U.S. This resource lists and briefly describes key actions in the order in which they were first issued, reported or announced, with subsequent linked actions and related outcomes also included with each entry. As new policy changes occur, they will be added.
This resource is not meant to be exhaustive of all administration actions related to public health, as many other federal policy changes – including outside of HHS – have public health implications but are not captured here.
Presidential Executive Orders precipitate removal of some HHS websites and health data. – In the first days of his second term President Trump issued a number of Executive Orders (EOs), including EOs that revoked many Biden administration orders and programs, and instituted new federal guidance related to “gender ideology,” “diversity, equity, and inclusion (DEI),” and “merit-based opportunities.” These EOs have implications for public health, particularly related to the collection and presentation of data and websites by the federal government. For example, in response to the EOs, HHS began to remove thousands of websites and numerous federal databases with public health information deemed to be related to DEI, LGBTQ, reproductive health, HIV/AIDS research, health disparities, and more, and limited some data collection and analysis in these areas. A lawsuit was filed to reverse these removals, and some information has been restored over time. In September, the administration agreed to restore all previously removed health-focused websites and data to versions that had existed on January 29, 2025.
February 7, 2025
NIH announces change to indirect cost rate guidance. – As part of grants for health research, the National Institutes of Health (NIH) provides “indirect cost” funding to grant recipients, which supports administration and facilities costs at grantee institutions. On February 7, NIH announced it would apply a new 15% “standard indirect cost rate” on all grants, which would apply to any new grants and to existing grants for expenses as of February 10, 2025. This was challenged in federal court and federal judges placed holds on the policy, first through a temporary restraining order affecting 22 states on February 10, a nationwide preliminary injunction on March 5, and a permanent injunction on April 4; prior rates still apply for the time being. The administration appealed the ruling and legal proceedings continue. If implemented, a 15% indirect cost rate would be a much lower rate compared to historical NIH rates and would amount to a significant cut in funding for institutions performing NIH-sponsored health research.
February 13, 2025
Robert F. Kennedy, Jr. confirmed as HHS Secretary under President Trump. – The Senate voted 52-48, along party lines, to confirm Robert F. Kennedy, Jr. as the Secretary of Health and Human Services.
February 13, 2025
President Trump issues Executive Order (EO) establishing MAHA policy agenda and MAHA Commission. – The EO outlines the purpose and objectives of the Trump administration’s Make American Healthy Again (MAHA) efforts. Stating that the U.S. must “re-direct our national focus…toward understanding and drastically lowering chronic disease rates and ending childhood chronic disease,” it directs federal agencies to “aggressively combat” mental health disorders, obesity, diabetes, and other conditions. It also establishes the MAHA Commission to advise the President, naming Secretary Kennedy as Chair. The EO directs the Commission to submit an assessment on how to combat the “childhood chronic disease crisis” within 100 days, and a strategy to address the crisis within 180 days, setting in motion processes to develop further public health strategies and plans (discussed in other entries below).
February 14, 2025
White House, DOGE initiate “reduction in force (RIF)”, including for HHS personnel. – The EO outlines the purpose and objectives of the Trump administration’s Make American Healthy Again (MAHA) efforts. Stating that the U.S. must “re-direct our national focus…toward understanding and drastically lowering chronic disease rates and ending childhood chronic disease,” it directs federal agencies to “aggressively combat” mental health disorders, obesity, diabetes, and other conditions. It also establishes the MAHA Commission to advise the President, naming Secretary Kennedy as Chair. The EO directs the Commission to submit an assessment on how to combat the “childhood chronic disease crisis” within 100 days, and a strategy to address the crisis within 180 days, setting in motion processes to develop further public health strategies and plans (discussed in other entries below).
February 14, 2025
President Trump issues Executive Order prohibiting federal funding to schools and universities with COVID-19 vaccine requirements. – The EO requires HHS to work with the Department of Education to prohibit COVID-19 mandates in schools, by issuing guidelines for compliance and barring federal funds from going to any educational agency, K-12 school, or institution of higher education that requires COVID-19 vaccination to attend in-person education programs (educational vaccine mandates are set at the state level). Educational vaccine requirements are set at the state and local levels. At the time the EO was released in February, no state required K-12 students to be vaccinated against COVID-19 while 15 colleges required Covid vaccines for students. However, by March 14, 2025 all of those colleges had ended their COVID-19 vaccine requirements for students.
February 18, 2025
Secretary Kennedy announces public health policy priorities during HHS welcome ceremony. – In his first remarks to HHS staff, Secretary Kennedy announces the public health priorities for his tenure. This include investigating the childhood vaccine schedule, tackling corruption and promoting transparency, and addressing a “chronic disease epidemic” especially in children, which he says may be linked to pesticides, food additives, antidepressants, microplastics, cellphone emissions, and other factors.
February 28, 2025
Secretary Kennedy issues new rule ending public comment requirement for HHS grants and contracts. – The new rule rescinds a prior HHS policy on “Public Participation in Rule Making” (the “Richardson Waiver,” dating back to 1971) and “re-aligns the Department’s rule-making procedures with the Administrative Procedure Act.” As a result, “matters relating to agency management or personnel or to public property, loans, grants, benefits, or contracts” are exempt from the notice and comment procedures. This removes what had been a key step in the rulemaking process requiring public notification and a comment period. For example, changes to HHS policies related to work requirements for Medicaid and NIH funding would no longer require public comments under the new rule. This could streamline implementation of HHS policy, but also reduce public visibility on changes before they take effect. Some lawmakers and public health focused groups have asked HHS to return to the prior requirements under the Richardson Waiver.
March 7, 2025
HHS announces that CDC will conduct a study of factors contributing to the rise in autism in the U.S. – In statements to the press, HHS officials indicate CDC will initiate a study looking at the factors that are contributing to the rise in autism diagnoses in the U.S.. To date, no new CDC study results on this topic have been released though in a related development, in September 2025 President Trump and HHS leadership announced at a press conference and through a White House Fact Sheet that they believe there is a link between acetaminophen (e.g., Tylenol) use in pregnancy to autism (further details provided below). President Trump and Secretary Kennedy both have a history of linking vaccines and autism, even though there is no evidence of such a link.
March 13, 2025
Food and Drug Administration (FDA) releases guidance on 2025-2026 influenza vaccine composition. – The FDA guidance identifies which influenza virus strains manufacturers should use as components of 2025-2026 influenza vaccines. To develop these recommendations, FDA convened meetings of federal scientific and public health experts, including from FDA, CDC, and Department of Defense, but did not consult with the FDA’s Vaccines and Related Biological Products Advisory Committee (VRBPAC) or other professional groups outside the government. FDA had canceled the scheduled VRBPAC meeting on this topic, and the lack of input from outside experts was a break from past years’ practices. In addition, in past years there was active participation and coordination between U.S. federal experts and global technical experts working under the auspices of the World Health Organization (WHO), but official communications with WHO-linked experts has been curtailed since the Trump administration announced in January 2025 that the U.S. was withdrawing its membership from the UN agency.
March 17, 2025
NIH initiates termination of numerous grants for HIV prevention and treatment programs. – The canceled NIH grants includesupport for researchers investigating use of PrEP, medication used pre-exposure to prevent HIV infections, and programs focused on HIV/AIDS in adolescents and young adults. Even as the first Trump administration supported HIV/AIDS prevention and treatment efforts, including through a highly visible federal effort to “end the HIV epidemic” in the U.S. by 2030, these same programs have now been targeted for cuts (further details below).
March 17, 2025
HHS removes Surgeon General warning declaring gun violence a public health crisis. – The HHS website was changed, removing a 2024 advisory from the Surgeon General on the public health impacts of gun violence. In addition to removing the Surgeon General’s warning, the administration has rolled back a number of gun safety policies in place during the Biden administration. The White House Office of Gun Violence Prevention, established during the Biden administration was shut down in early 2025. Further, significant numbers of staff at CDC’s Injury Center, which collects data on violent deaths and injuries, and CDC’s Division of Violence Prevention have been let go as part of the Trump administration’s reduction in force efforts.
March 25, 2025
HHS and CDC seek to pull back $11 billion in supplemental COVID-19 and public health funding from state and local health departments. – In a statement, HHS says it intends to pull back $11.4 billion in supplemental funding that had been provided by Congress for state and local public health departments through CDC for pandemic response activities. Following the announcement, on April 1, a group of 23 mostly Democratic-led states sued the Trump administration over the attempt to pull back this funding. On April 3, a federal judge placed a temporary block on the administration’s actions, and on May 16, another federal judge indefinitely blocked the administration from enacting its funding pull back for the states that are part of the lawsuit. As of late August 2025, almost 80% of the funds initially targeted for cuts by the Trump administration had been restored for the 23 states that won in court. However, funding has not been restored to the remaining states, the majority of which are Republican-led.
March 27, 2025
HHS announces a major re-organization and job cuts plan. – HHS announces plans for a major restructuring of the department, in accordance with President Trump’s February 26 EO on “Implementing the President’s ‘Department of Government Efficiency’ Workforce Optimization Initiative.” The announcement says HHS will create an Administration for a Healthy America (AHA), which would combine several existing HHS offices including the Office of the Assistant Secretary of Health (OASH, which contains the Surgeon General’s Office), the Health Research and Services Administration (HRSA), the Substance Abuse and Mental Health Services Administration (SAMSHA), the Agency for Toxic Substance and Disease Registry (ATSDR), and the National Institute for Occupational Safety and Health (NIOSH). In addition, the Administration for Strategic Preparedness and Response (ASPR) at HHS would be moved under CDC. The announcement also says HHS will reduce its workforce by eliminating 10,000 full-time positions. Combined with other reduction in force efforts, a total of 20,000 HHS workers are expected to lose their jobs.
On May 5, a coalition of 19 Democratic-led states and the District of Columbia filed a lawsuit against the mass firing of federal health workers and re-organization of HHS. On May 10, a court ordered a temporary pause on sweeping federal firings at HHS and other agencies. On July 1, a federal judge blocked mass firings at HHS, saying they are likely unlawful. However, on July 8 the Supreme Court overturned the lower court decisions, allowing the Trump administration to proceed with job cuts. As of August it is estimated that over 20,000 jobs at HHS have already been cut, meaning the administration already met its initial workforce reduction goal.
Regarding re-organization, some organizational changes have been implemented at HHS, with major cuts or closures to public health related offices such as the HHS Office of Infectious Diseases & HIV Policy, the HHS Office of Minority Health, and HRSA’s Bureau of Primary Health Care. However, other proposals such as the formation of an Administration for a Healthy America (AHA), have not yet been implemented. Implementing AHA to the extent proposed is likely to require approval from Congress, though so far Congress has not acted on legislation codifying these proposals.
March 31, 2025
HHS withholds portion of Title X family planning service grants. – HHS notifies one in five current grantees of the federal Title X family planning program that a portion of their funding would be temporarily withheld. This funding freeze affects all nine Planned Parenthood grantees, in addition to 7 other nonprofit grantees, and it is estimated that a total of 879 clinics (24% of all Title X clinics) in 23 states are affected. After several months, funds were reinstated to some organizations, but the Planned Parenthood grantees have still not had their funding reinstated.
April 1, 2025
HHS ends federal support for the “Safe to Sleep” program, which focuses on prevention of infant deaths during sleep. – The Trump Administration ends federal participation in Safe to Sleep, a national campaign that focused on educating parents of newborns about safer sleeping practices for infants that can prevent death. The program, supported through the NIH’s National Institute of Child Health and Human Development (NICHD) Office of Communications in recent years, had been in existence for over 30 years and had contributed to a major decline in sudden infant deaths. The NICHD office was eliminated on April 1, along with federal support for “Safe to Sleep.”
April 2, 2025
HHS requires CDC to reduce contract spending by $2.9 billion as part of DOGE cost reduction efforts. – According to reports, HHS orders CDC to reduce its contract spending by $2.9 billion by April 18.CDC contract funding has been used to support several services at the agency including security, cleaning, and computers/technology. The sudden requirement to cut this spending by approximately 35% affects CDC operations.
April 7, 2025
HHS Secretary Kennedy announces changes to fluoride policies. – Secretary Kennedy announces a plan to implement a number of changes to federal policy related to water fluoridation, including stating that CDC will stop recommending water fluoridation as a public health intervention (though to date, HHS and CDC still recommend community water fluoridation). In addition, Kennedy says the defunct Community Preventive Services Task will be revived and reconvened, with a goal of studying and making recommendations about water fluoridation. Kennedy also called on states to ban fluoride in their drinking water. Already this year Utah and Florida have banned community water fluoridation, the first states ever to do so.
April 17, 2025
FDA informs Pfizer/Moderna that mRNA COVID vaccines will require an expanded warning label about myocarditis. – In letters sent April 17, the FDA informs Pfizer and Moderna they must alter the warning labels for their COVID-19 mRNA vaccines to include expanded risks for myocarditis and pericarditis. Previously, the warning labels for these vaccines noted risks for these conditions for those aged 18 to 24 years (Moderna) and 12 to 17 years (Pfizer). However, updated labels are required to include new language saying “the observed risk of myocarditis and pericarditis following vaccination with mRNA COVID-19 vaccines has been highest in males 12 through 24 years of age” and that “persistence of abnormal cardiac magnetic resonance imaging (CMR) findings that are a marker for myocardial injury was common.” According to FDA, the labels must also include more information about these conditions and their health risks. Since the letters were sent, the companies have complied with the new FDA requirements. FDA approved the updated label language on June 25.
April 22, 2025
FDA and HHS announce measures to phase out use of petroleum-based food dyes. – FDA and HHS announce a series of steps the federal government will take to remove petroleum-based synthetic dyes from the U.S. food supply. These actions include initiating a process to revoke federal authorization for two such dyes and planning phase-outs by the food industry for others. In addition, the government will support research on food additives and children’s health and authorize natural alternative coloring options. Under the current plan, the phase-outs will occur through voluntary action taken by food companies.
May 1, 2025
HHS announces a $500 million investment in a “next generation universal vaccine platform.” – HHS and NIH announce that $500 million in funding will be directed to a new effort to develop a “universal vaccine platform for pandemic-prone viruses.” The platform uses inactivated whole viruses, and is part of a broader federal effort to develop universal vaccines called “Generation Gold Standard.” The funds for this new investment appear to be re-purposed vaccine development funds from the Biden Administration’s NextGen initiative to develop next generation COVID-19 vaccines.
May 2, 2025
White House Releases FY 2026 President’s Budget Request calling for major fundings cuts at HHS. – The White House released an outline of the administration’s budget request for FY2026 and on May 30, the White House submitted the full Budget Request for FY2026 to Congress. The request proposes steep cuts to the HHS budget, including cuts for CDC, HRSA, SAMHSA, NIH, eliminating the Hospital Preparedness Program at ASPR, and reducing funding and cutting some programs focused on HIV/AIDS research and response. The budget request also asks Congress for $500 million to support a new “Administration for a Healthy America (AHA)” and MAHA-related priorities. The President’s Budget Request is only a proposal, as it is Congress that ultimately decides how much money the federal government appropriates. So far, Congressional spending bills for FY2026 have not included cuts to HHS of the magnitude requested by the President, and Congress has not provided the requested $500 million for AHA though budget negotiations continue.
May 5, 2025
White House Executive Order restricts funding and increases oversight for “gain of function” research at HHS. – In an EO titled “Improving the Safety and Security of Biological Research” the White House cites concerns with federally funded “gain-of-function” (GOF) research on biological agents and states the Biden administration allowed dangerous GOF research to occur without sufficient oversight. The EO directs the Secretary of HHS to coordinate with other relevant Executive branch offices to establish guidance to end federal funding of “foreign entities” where GOF is being undertaken or in countries lacking oversight of GOF research. The EO requires the relevant Executive offices to submit updated policies and guidance for all federally supported GOF-related research, and to develop a strategy for managing risks of non- federally funded GOF research. The full implications of the EO are not yet clear, as the Executive branch offices must develop and implement specific guidance and regulations. According to outside experts, potential benefits of the EO include more transparency and stricter enforcement of dangerous research, while potential risks include hindering beneficial research that is not GOF and researchers choosing to curtail beneficial research to avoid potential repercussions under evolving federal restrictions.
May 20, 2025
FDA leaders announce clinical trials will be needed for approval of certain new COVID vaccine formulations. – In a medical journal article, FDA leaders indicate that going forward, for federal approval of new or updated COVID-19 vaccines (“boosters”) for use in individuals who are not considered at higher risk (defined as persons 65 or older or those with certain health conditions), will require vaccine makers to present evidence from randomized, placebo-controlled trials that demonstrate safety and efficacy. The announced policy is a departure from prior years when FDA did not require new trial data to authorize or approve boosters, but instead allowed approvals based on immune response evidence. The new policy could hinder investments by pharmaceutical companies in developing new COVID vaccine formulations, given the greater expense and time required to conduct new, full clinical trials.
May 22, 2025
MAHA Commission Report on childhood chronic disease published. – The first official report from the MAHA Commission (established by the February 13 EO discussed above) discusses factors contributing to a “chronic disease crisis” for U.S. children and provides a “call to action”. The report highlights four main drivers of the crisis: poor diet (primarily due to consumption of ultra-processed foods), exposure to chemicals, lack of physical activity and chronic stress, and “overmedicalization (excessive use of prescription drugs, such as antidepressants). The report calls for federal agencies to “close critical research gaps and guide efforts to better combat” these issues. It also says the MAHA Commission will develop and release a strategy in August (discussed below). The report expanded on the ideas initially outlined in the February EO and provided more details on Secretary Kennedy’s priorities to address chronic disease in children. There was some criticism of the report after its publication, with experts questioning some of the evidence and conclusions and pointing out significant errors and studies cited that did not exist, which indicated that artificial intelligence was likely used to help write the report.
May 23, 2025
Administration ends NIH funding for several HIV vaccine research projects. – NIH notifies two grant recipients working on broadly neutralizing antibody research for HIV vaccines of the cancelation of their funding. The canceled grants supported early-stage vaccine development research that uses a different approach than other HIV vaccine candidates. Some other HIV vaccine candidates remain in the development pipeline and clinical trials continue, but the absence of this early-stage research could jeopardize the development of additional candidates going forward.
May 27, 2025
HHS Secretary Kennedy announces CDC will no longer recommend COVID vaccines for healthy pregnant women and children. – In a video post on X, Secretary Kennedy announces “the COVID vaccine for healthy children and healthy pregnant women has been removed from the CDC recommended immunization schedule.” The announcement was a departure from the typical process for changing vaccine recommendations, which includes review and input from the Advisory Committee on Immunization Practices (ACIP) and a notification from the CDC Director. Initially, the implications of changing CDC guidance without ACIP input were unclear given that no-cost insurance coverage for vaccination is linked to ACIP and CDC recommendations. On May 30, CDC changed the language on its website for COVID-19 vaccines, removing its prior recommendation for pregnant women to be routinely vaccinated and stating that healthy children 6 months to 17 years old could be vaccinated in consultation with health care providers/parents – a recommendation known as “shared decision-making,” which would mean insurance would still have to cover such vaccinations. On July 7, a coalition of professional medical organizations filed a lawsuit against HHS over the new COVID-19 vaccine recommendations, saying the department did not follow federal procedures in making the change and also mislead the public on the issue (on January 6, 2026, a federal court confirmed these plaintiffs have standing to challenge HHS’s actions on the COVID-19 vaccine recommendations, allowing the case to proceed to arguments). On August 19, independent expert groups, including the AAP, issued their own recommendations for COVID vaccines in infants and young children in contrast with CDC’s new recommendations. On Aug 22, ACOG issued their own recommendations for pregnant patients.
June 9, 2025
HHS Secretary Kennedy announces removal of all sitting members of ACIP. – In a post on X and a subsequent HHS press notice, Secretary Kennedy announces that all 17 sitting members of the CDC’s Advisory Committee on Immunization Practices (ACIP) are dismissed, to be replaced with new members selected by the Secretary. Kennedy says the move is “prioritizing the restoration of public trust above any specific pro- or anti-vaccine agenda.” The HHS Secretary does have the discretion to remove and nominate ACIP members, though no previous Secretary has dismissed all ACIP members at once. In a subsequent X post on June 11, Kennedy announces the nomination of eight new members to ACIP, several of whom have been critical of COVID-19 vaccines and have expressed concerns about harms caused by vaccinations more generally. In a later press release from September 15, HHS announces five more members to be appointed to ACIP, including several with a history of criticism of COVID-19 vaccine policies.
June 17, 2025
FDA announces National Priority Vouchers for expedited regulatory review of new drugs that support “U.S. national interest.” – FDA announces a Commissioner’s National Priority Voucher (CNPV) program, which can be “redeemed by drug developers to participate in a novel priority program” that shortens regulatory review time from 10-12 months to 1-2 months. FDA says it will determine the availability of vouchers for companies that are aligned with the “national health priorities” of: addressing a health crisis in the U.S.; delivering more innovative cures for the American people; addressing unmet public health needs; and, increasing domestic drug manufacturing as a national security issue. On October 16, FDA announced the first nine CNPV recipients, and on November 6, announced six more recipients. The impact of this new priority voucher program on speeding drug approvals and onshoring drug manufacturing capacity is as yet unclear. In addition, there are several other existing priority review processes at FDA so adding another could strain FDA staff capacity at the same time there has been significant reductions in FDA’s staff and budget. These strains have already slowed FDA review times in general.
June 18, 2025
FDA approves lenacapavir – a new HIV prevention drug. – FDA approves Gilead Sciences’ lenacapavir, a new injectable PrEP drug that has been shown to be highly effective at preventing HIV infection, and which requires just one dose every 6 months, making it the first ever twice-a-year drug option for HIV prevention. In September, CDC issued clinical guidance for use of injectable lenacapavir as PrEP, though that guidance did not include reference to transgender people, a group intentionally included in the clinical trials and at increased risk of HIV. FDA’s approval also precipitated a review by the World Health Organization (WHO) and on October 6, WHO pre-qualified lenacapavir for prevention of HIV. WHO pre-qualification can speed regulatory approval for the drug in many low- and middle-income countries with a high burden of HIV/AIDS and can also allow for global health mechanisms like the Global Fund to Fight AIDS, Tuberculosis and Malaria to procure the drug.
June 25-26, 2025
The newly reconstituted ACIP makes recommendations and policy changes related to RSV and influenza vaccines, and designates new workgroups on hepatitis B, MMRV, and the childhood immunization schedule. – ACIP votes to recommend respiratory syncytial virus (RSV) injections for babies and RSV vaccine for people 50 and older, and a ban on the use of thimerosal in multi-dose influenza vaccine vials. ACIP also agrees to stand up three new workgroups that will review the U.S. childhood vaccination schedule, hepatitis B guidance, and combination MMRV vaccine. Subsequently, on July 3, CDC issued new RSV guidance that mirrored ACIP recommendations. On July 23, Secretary Kennedy enacted ACIP’s recommendation on thimerosal, rescinding federal recommendations for any influenza vaccines containing thimerosal (a change that only affects a very small percentage of the overall influenza vaccine market that is comprised of multidose vials).
July 1, 2025
HHS alters program requirements and withholds funding from sex education and teen pregnancy prevention programs. – HHS notifies all Teen Pregnancy Prevention (TPP) program grantees and Personal Responsibility Education Program (PREP) grantees in 46 states and territories that their material must align with President Trump’s executive orders, including those that ban the promotion of gender inclusivity, risk losing federal funding. TPP is a national grant program that funds grantees to replicate, develop, test, and evaluate evidence-based approaches to prevent teen pregnancy, while PREP awards grants to state agencies to use evidence-based models in educating adolescents on both abstinence and contraception. In August, the Trump administration cancelled a $12.3 million PREP grant to California after state officials refused to revise curricula in compliance with the EOs. In September 2025, 16 states and D.C. sued HHS alleging that the new PREP grant conditions are unlawful, unconstitutional, and harmful to gender diverse youth. Similarly, a federal judge blocked the HHS policy changes for TPP in October 2025.
July 2, 2025
CDC deactivates its emergency response for H5N1 influenza (bird flu) and limits tracking and reporting of data on bird flu infections in humans and animals. – CDC ends its emergency response for H5N1 bird flu in the U.S., which had been active since April 4, 2024. CDC reports the change is due to a decline in animal infections and no reports of human cases since February 2025. CDC also says data on the number of people tested for H5N1 will be reported only monthly, and no further data on infection rates in animals will be reported on the CDC website. Even so, reporting from states showed the number of H5N1 cases in birds, which had declined over the summer, began to increase again in fall 2025. However, much of the federal research and response efforts for H5N1 have been closed down or significantly limited following funding and staff cuts and a prolonged government shutdown. The limited federal tracking and reporting of H5N1 infections can slow identification of outbreaks and potentially slow response times.
July 9, 2025
HHS Secretary Kennedy cancels a scheduled meeting of the U.S. Preventive Services Task Force (USPSTF). – Secretary Kennedy cancels a meeting of the USPSTF several days before it was scheduled to take place, with no reason given and no re-scheduled meeting date provided. Typically, the task force meets three times a year, though no meeting has yet occurred under Secretary Kennedy. USPSTF is responsible for reviewing and recommending preventive health services. USPSTF recommendations have implications for what services insurers must cover with no cost-sharing, under the Affordable Care Act (ACA). Such services can include screening tests, behavioral counseling, and medications that can prevent diseases and illness (other than vaccines, which are tied to ACIP recommendations). However, along with other parts of the ACA, USPSTF has faced court challenges. On June 27 (prior to Kennedy’s cancelation of the meeting), while the Supreme Court ruled the ACA requirement that insurers cover USPSTF-recommended services is indeed constitutional, it also found that the HHS Secretary has the power to add and remove USPSTF members at will, which underscores the possibility that Secretary Kennedy may choose to dismiss some or all of the existing USPSTF members and appoint new members (as Kennedy has done with ACIP), or simply not name any new members, and has the power to choose not to adopt USPSTF recommendations. In light of Kennedy’s cancellation and the Supreme Court ruling, 104 public health focused organizations called on Congress to “protect the integrity of the USPSTF” through legislative action. The subsequent USPSTF meeting was scheduled to occur in November but that was also canceled, with HHS citing the government shutdown as the reason. Meetings in March 2026 and July 2026 were also canceled.
July 31, 2025
FDA announces new safety label requirement for opioid pain medications. – The FDA says will require safety labels on opioid medications so that users can better understand that risks of long-term opioid use. The updated labels should include a summary on the risk of addiction, misuse, and overdose, treatment guidance and the risk of higher doses, how to safely discontinue opioid use, drug interactions, digestive complications, and overdose reversal medications. Drug companies received notification letters and have 30 days to submit updated labels for review.
July 31, 2025
HHS Secretary Kennedy swears in Susan Monarez as CDC Director. – In a statement welcoming the newly Senate-confirmed CDC Director, Secretary Kennedy says Monarez has “unimpeachable scientific credentials” and he has “full confidence in her ability to restore the CDC’s role as the most trusted authority in public health.” However, 28 days later (on August 27) the White House removed Monarez from her position at CDC. According to Kennedy, she was removed because he lost trust in her ability to serve as CDC Director and to implement the policies of the Trump Administration. According to Monarez, she was removed because she would not provide “blanket approval” for vaccine policy changes in advance and would not fire, as requested by Kennedy, CDC employees without cause. On August 28, Secretary Kennedy announced in a letter to CDC staff that Deputy Health and Human Services Secretary Jim O’Neill would serve as acting CDC Director.
August 1, 2025
Newly announced CDC policy prevents outside professional medical and public health organizations from participating in working group meetings of ACIP. – Officials at HHS notify professional medical organizations such as the American Academy of Pediatrics (AAP), the American Medical Association (AMA), the American College of Obstetricians and Gynecologists (ACOG), and others that they will be excluded from joining ACIP working group discussions going forward. Professional groups representing medical doctors and other stakeholders in vaccine policies have long participated as non-voting members, including in ACIP working groups. Working groups are typically responsible for helping review available data about topics prior to ACIP meetings, and helping develop recommendation language for ACIP to vote on, as well as other activities in support of ACIP. While the outside groups can be present and can participate in full ACIP meetings, the new policy removes them from providing any input through working groups.
August 5, 2025
HHS announces a “coordinated wind down” of $500 million in federal funding for mRNA vaccine research. – HHS announces that it will cancel and begin to wind down mRNA vaccine development activities funded through the Biomedical Advanced Research and Development Authority (BARDA). In total, HHS reports it is canceling 22 projects worth nearly $500 million because “these vaccines fail to protect effectively against upper respiratory infections like COVID and flu…Going forward, BARDA will focus on platforms with stronger safety records and transparent clinical and manufacturing data practices.” mRNA COVID-19 vaccines are effective in preventing severe illness and death from the disease, and mRNA vaccine technology has potential applications for other infectious diseases, as well as chronic diseases like cancer. The cancellation removes the bulk of U.S. federal funding for mRNA research, leaving questions about future progress by the U.S. in this area of vaccine technology.
August 15, 2025
HHS reinstates the defunct Task Force on Safer Childhood Vaccines. – The original Task Force on Safer Childhood Vaccines, a federal panel created by Congress in 1986 “to improve the safety, quality, and oversight of vaccines” was disbanded in 1998, but HHS announces that the group will be re-instated at NIH with participation from officials at FDA, CDC, and other government agencies. The goal of the reconstituted Task Force will be “the development, promotion, and refinement of childhood vaccines that result in fewer and less serious adverse reactions than those vaccines currently on the market, and improvements in vaccine development, production, distribution, and adverse reaction reporting” to help increase federal oversight and investigation of vaccine injuries. The Task Force will come together to develop recommendations to be submitted to Congress within two years, with updates every two years after. Reinstatement of this panel has been a goal of anti-vaccine advocates for years, including the Children’s Health Defense, the anti-vaccine organization Secretary Kennedy founded, which supported a lawsuit earlier in 2025 against Kennedy that sought to require him to reconvene the Task Force.
August 27, 2025
FDA approves COVID-19 vaccines for 2025-2026, while limiting scope of approval to certain ages and risk profiles. – FDA approves updated COVID-19 vaccines for 2025-2026, but also limited the approval to persons 65 and older and those between 18 and 64 with a health condition that puts them at higher risk for severe disease. Previously, the FDA had approved the use of vaccines for all ages (over 6 months) regardless of risk profile.
September 9, 2025
MAHA Commission releases strategy to address childhood chronic disease. – A new MAHA Commission strategy document outlines actions the federal government is taking or plans to take to address childhood chronic disease in the U.S. These include “more than 120 initiatives” that together represent “the most ambitious national effort ever to confront childhood chronic disease,” and which outline a “blueprint for the entire government” to address chronic disease. Elements of the strategy include: changing federal science and research priorities, reforming dietary guidelines, changing nutrition and food regulations through reducing additives and ultra-processed foods, and improving effort to raise public awareness about chronic disease. The strategy highlights the risks of vaccine injuries, fluoride in drinking water, among many other areas.
September 18, 2025
Secretary Kennedy renews the declaration of the national opioid crisis as a public health emergency. – In a declaration on an HHS website, Secretary Kennedy renews the declaration of the opioid crisis as a national public health emergency (PHE). The opioid crisis was initially declared a public health emergency in 2017; renewal is required every 90 days to continue the PHE.
September 19, 2025
Secretary Kennedy announces that the FDA will launch a new review of mifepristone. – Secretary Kennedy announced that the FDA will undergo a review of the current Risk Evaluation and Mitigation Strategy (REMS) for mifepristone, due to new evidence including an April 2025 report from the Ethics and Public Policy Center (EPPC) which claims that mifepristone has a higher rate of adverse events than previously reported. This report has drawn criticism due to methodological flaws and lack of transparency regarding its data sources.
September 19, 2025
ACIP makes several new recommendations related to MMRV and COVID-19 vaccines. – In its September 18-19 meeting, ACIP members vote on several new recommendations including to no longer recommend the combination MMRV (measles, mumps, rubella, and varicella) vaccine for children under the age of 4 and instead to recommend that children in this age group receive measles, mumps, and rubella (MMR) vaccine separately from the varicella vaccine (V). In addition, ACIP members vote to change what had been a universal COVID-19 vaccine recommendation (except for HHS’ recent change for healthy children and pregnant women) to “shared clinical decision-making”, including for those 65 and older, along with a recommendation for new language on risk-benefit for COVID-19 vaccinations. ACIP’s recommendations were adopted by CDC on October 6. While the separate MMR+V vaccines had been recommended as preferred by the CDC for many years, the combination MMRV provided an option for parents to reduce the number of injections their children receive. Now, insurers will no longer be required to cover this vaccine at no-cost. The new COVID-19 vaccine recommendations mean people of all age groups are now recommended to have an interaction with a health care provider (which could include a doctor, nurse, or pharmacist) to determine whether getting a COVID-19 vaccination is recommended for them. If that determination is made, insurers must cover the vaccine at no-cost, although it is possible that some consumers may face challenges in accessing providers in the first place or demonstrating that they have consulted with a medical provider seeking vaccination in some cases.
September 22, 2025
President Trump and Secretary Kennedy announce new actions to address autism spectrum disorder in the U.S. – In a press conference and via an HHS press statement and Fact Sheet, President Trump and HHS Secretary announce several actions to address the issue of autism spectrum disorder (ASD) in the U.S. This includes FDA authorization for leucovorin, a treatment option for some children with autism, a regulatory change that will allow state Medicaid programs to newly cover leucovorin for the indication of ASD. President Trump and Secretary Kennedy also highlight what they say are risks of acetaminophen use during pregnancy and association with autism. The press release notes “HHS wants to encourage clinicians to exercise their best judgment in use of acetaminophen for fevers and pain in pregnancy by prescribing the lowest effective dose for the shortest duration when treatment is required.” In his remarks, President Trump also implicated childhood vaccines as a potential risk factor for autism, though no new evidence was presented and that link has already been repeatedly and conclusively ruled out. In a subsequent press statement on September 22, HHS announced FDA was initiating a labeling change for leucovorin, and a safety label change for acetaminophen to include information about the “potential risks of acetaminophen so patients can make a more informed decision.” Public health groups and experts criticized the conclusions linking acetaminophen use in pregnancy and autism, and expressed doubts about leucovorin as a treatment for autism. President Trump’s remarks also precipitated a lawsuit filed on October 28 in Texas against the maker of Tylenol.
September 30, 2025
FDA approves a new generic mifepristone product. – The FDA approved Evita’s Solutions application for a generic version of mifepristone. The approval included a reminder that the generic mifepristone is subject to the same Risk Evaluation and Mitigation Strategy (REMS) as the brand-name.
September 30, 2025
HHS awards $60 million in grants to support prevention of falls and related programs for older adults and those with disabilities. – Secretary Kennedy announced 59 new grants totaling $60 million is being awarded to states, territories, tribes, and local organizations supporting older adults and Americans with disabilities, including programs for “preventing falls among seniors, managing chronic conditions…and funding dementia-capable programs.”
October 10, 2025
Trump Administration fires thousands of HHS employees, including hundreds at CDC, during federal government shutdown. – In the midst of a government shutdown and an ongoing federal funding impasse in Congress, the White House Office of Personnel and Management saysover 4,000 federal workers are to be fired. At HHS, over a thousand workers are notified that they have lost their jobs, with most of those losses concentrated at CDC. Some of those job losses were reversed over the next few days, with HHS officials stating some notices were sent in error. Even so, as of October 14 it is estimated that about 600 CDC employees remain fired, including staff in areas such as injury prevention, health statistics, and Congressional relations. There is a question about whether such firings during a government shutdown are legal, and groups representing federal workers have filed lawsuits to halt these mass layoffs.
October 31, 2025
FDA announces new restrictions on ingestible fluoride products for children. – FDA announces new enforcement actions “to restrict the sale of unapproved ingestible fluoride products for children” and sends letters to health care professionals warning about the risks associated with these products. The actions come after FDA conducted a review and published a scientific evaluation of these products. In the announcement. FDA says it will be developing a “fluoride research agenda” and “the first national oral health strategy” for the U.S. in partnership with NIH and other HHS agencies.
November 10, 2025
FDA announces a warning label change on hormone replacement therapy (HRT) products for addressing symptoms of menopause. – In a press release, a fact sheet, and a live press event, FDA leaders announce that they will initiate the removal of broad “black box” warnings from HRT products for menopause. The FDA also announces approvals for two new drugs for menopausal symptoms. According to the FDA, women have been “under-utilizing approved therapies” since the “black box” warnings about risks associated with the drugs were placed on these products over 20 years ago. Labels will be rewritten with guidance saying that there are long-term health benefits if HRT is begun within 10 years of the onset of menopause.
November 19, 2025
CDC changes language on its website to say a link between vaccines and autism cannot be ruled out. – A CDC website providing information to the public on Autism and Vaccines, is changed to include language saying “studies have not ruled out the possibility that infant vaccines cause autism.” The new site also discusses the “state of the evidence” on common childhood vaccines and supposed links to autism. The new language is a reversal from previous CDC statements saying “vaccines do not cause autism,” and contradicts the long established scientific consensus that there is no link between vaccines and autism. The new CDC webpage language has been criticized by professional medical organizations such as the American Medical Association and the American Academy of Pediatrics, as well as autism organizations such as Autism Speaks and the Autism Science Foundation.
November 21, 2025
CDC staff ordered to end all monkey research programs, potentially affecting development of prevention tools for HIV and other infectious diseases. – According to reports, CDC staff are ordered to halt its monkey research program by the end of 2025. This program has helped develop HIV prevention tools such as pre-exposure prophylaxis (PrEP) and microbicides, as well supported prevention research for other infectious diseases.
November 28, 2025
Internal FDA communication proposes stricter federal requirements for testing and approving vaccines. – According to reports, the head of FDA’s Center for Biologics Evaluation and Research (CBER), which is responsible for regulating vaccines, issues an email to staff proposing new, stricter federal requirements for vaccine testing, evidence, and approval. The email states that in the future FDA will “demand pre-market randomized trials assessing clinical endpoints for most new products” and that FDA “will not be granting marketing authorization to vaccines in pregnant women” without this kind of evidence. Newly developed pneumonia, influenza, and COVID-19 vaccines are specifically mentioned as vaccines that would be subject to these new requirements. The rationale given for this policy change is a new analysis of vaccine safety data indicating “COVID-19 vaccines have killed American children,” though no evidence to support that statement is provided in the email.
December 5, 2025
ACIP votes to end recommendation that all newborns receive hepatitis B vaccine dose at birth On the second day of the Advisory Committee on Immunization Practices’ (ACIP) December 4-5 meeting, members vote to end a long-standing recommendation that all newborns in the U.S. receive a dose of hepatitis B vaccine. The committee now recommends parents of infants born to mothers who test negative for hepatitis B consult with their provider to help decide if and when their child should receive the first hepatitis B dose. ACIP continues to recommend that infants born to mothers who test positive for hepatitis B, or whose hepatitis B test status is unknown, receive the first hepatitis B vaccine dose at birth. A recommendation from ACIP becomes part of the official CDC immunization schedule once it is adopted by the CDC director.
December 30, 2025
HHS ends certain requirements for state reporting of immunization data to the Centers for Medicare and Medicaid Services (CMS). A December 30 letter from the Centers for Medicare and Medicaid Services (CMS) informs state health officials that starting in 2026, states will no longer be required to report several measures related to immunization status to CMS. Specifically, CMS removes the following from its “Child and Adult Core Sets”: “Childhood Immunization Status”, “Immunizations for Adolescents”, “Prenatal Immunization Status: Under Age 21”; and “Prenatal Immunization Status: Age 21 and Older.” In addition, in its letter CMS informs state health officials it will “explore options to facilitate the development of new vaccine measures that capture information about whether parents and families were informed about vaccine choices, vaccine safety and side effects, and alternative vaccine schedules” and “how religious exemptions for vaccinations can be accounted for.” Data reported by states and included in the Child and Adult Core Sets are used by Medicaid and CHIP to monitor access to and quality of health care for their beneficiaries, so an absence of this data could make monitoring immunization coverage in this population more challenging.
January 5, 2026
HHS announces changes to the federal childhood vaccination schedule that reduce the number of routinely recommended vaccines Health and Human Services (HHS) issues a memo implementing major changes to the government’s recommended vaccination schedule for children. Under the new guidelines, there are vaccines for 11 diseases recommended for all children, down from 17 diseases a year ago. In addition to COVID-19 (which HHS stopped recommending for all children back in October 2025), the new schedule no longer recommends routine vaccinations for five other diseases: rotavirus, COVID-19, influenza, hepatitis A, hepatitis B, and meningococcal. These vaccines have been moved from routine recommendation to “shared clinical decision making,” a process that is “individually based and informed by a decision process between the health care provider and the patient or parent/guardian.” The HPV vaccine remains recommended for routine vaccinations, though under the new guidelines HHS reduces the number of recommended doses of HPV drops from two or three (depending on age of initial vaccination) to one. Coverage for all of these immunizations should remain the same through public and private insurance mechanisms. On March 16, 2026, a federal judge issued a ruling that stayed changes to the vaccine schedule from being implemented, as the government did not follow required procedures. On April 29, HHS appealed the judge’s stay and court review continues.
February 3, 2026
BARDA opens solicitations for a $100 million prize program for development of novel antivirals targeting dengue, West Nile, and other viruses. In a news release, HHS’ Biomedical Advanced Research and Development Authority (BARDA) announces it is opening solicitations for a share of a new $100 million SMART Antiviral prize intended to speed the development of “broad-spectrum, small-molecule antiviral therapies” targeting families of viruses that include dengue, Zika, West Nile, and Chikungunya. This first stage is designed to receive solicitations at the concept stage, with solicitations for further development stages anticipated in the future.
February 4, 2026
Trump Administration instructs CDC to rescind $600 million in public health funds going to four Democratic-led states According to reports, the Office of Management and Budget ordered CDC to cut $600 million in funding that had been earmarked for state and local public health programs in California, Colorado, Illinois, and Minnesota. Most of the funding cuts affect programs focused on HIV and STD prevention, are are to be terminated because they “do not reflect agency priorities” according to an HHS spokesperson. On February 11, affected states filed a lawsuit in federal court against these cuts, and on February 12 a federal judge issued a temporary restraining order blocking the cuts from taking effect.
February 10, 2026
FDA refuses to review Moderna’s license application for its investigational mRNA-based influenza vaccine Moderna announces it received a “Refusal to File” letter from FDA stating that the agency will not initiate a review of the company’s biological license application for its investigational mRNA-based seasonal influenza vaccine. According to FDA, the refusal is due to the company’s use of an inadequate comparison arm in its study. Moderna states the letter is “inconsistent with previous written communications” with FDA staff. On February 18, Moderna announced that FDA had reversed its decision, and will now review the application, following further discussions with the company.
February 18, 2026
FDA to allow drug approvals with evidence from one clinical trial rather than two In an opinion article published in the New England Journal of Medicine, FDA leaders announce a new FDA policy that will make the default requirement for FDA approvals to be results from one clinical trial instead of the prior requirement of two clinical trials. The stated goal of the change is to accelerate the approval and availability of new medicines.
February 19, 2026
CDC delays February ACIP meeting HHS/CDC announces the ACIP meeting previously scheduled for February 25-27 will be postponed. The postponement occurs amid an ongoing federal lawsuit filed by the American Academy of Pediatrics (AAP) and other medical groups that argues the recent revisions made by HHS to the federal child immunization schedule were arbitrary and violated administrative procedures and seeks to have the ACIP panel appointed by HHS Secretary Kennedy removed and replaced and its decisions overturned. On February 26, CDC announced the ACIP meeting had been rescheduled for March 18-19. On March 16, 2025, the judge ruled that 13 of 15 ACIP member appointments did in fact violate administrative procedures and their appointments are stayed along with any ACIP votes since the appointments were made. As a result, the planned March 18-19 ACIP meeting has been canceled.
February 23, 2026
FDA launches new framework for speeding development and approval of therapies for rare diseases FDA announces draft guidance for drug developers that seek approval for targeted, individualized therapies. The new framework outlines new approaches to regulatory review and evidence requirements on the safety and efficacy for rare diseases, given that traditional randomized clinical trials may not be feasible for these conditions.
March 4, 2026
HHS Postpones Third Straight Meeting of US Preventive Services Task Force (USPTF) USPTF, which makes recommendations on preventive health care services, has not met since March of 2026. Five of the 16 USPTF members’ terms have ended as of January 1 and have not been replaced.
April 10, 2026
HHS Publishes Updated ACIP Charter The Trump Administration published an updated version of the Advisory Committee on Immunization Practices (ACIP) charter. The revised charter features language that broadens the inclusion criteria for ACIP member expertise, including mentions of vaccine safety and recovery from serious vaccine injuries as areas of expertise that members can possess. The charter language was updated yet again in May, with the newest version published on May 27, 2026. The newest version places oversight of ACIP more directly under the CDC director, includes language that emphasizes potential gaps or limitations in vaccine data, and does not commit to a set schedule of ACIP meetings annually (previously, the charter required three ACIP meetings a year).
April 22, 2026
CDC Study on COVID-19 Vaccine Effectiveness Held Back From Publication Reports find that Jay Bhattacharya, who is overseeing CDC operations while the Director position remains unfilled, held back publication of a CDC study on the effectiveness of the COVID-19 vaccine over the 2025-2026 winter season. The study was scheduled to be published in the CDC’s flagship MMWR publication on March 19, but Bhattacharya objected to the study’s design, although it is a very common design that has been used to study vaccine effectiveness in dozens of prior published studies. The study had found vaccination cut the likelihood of emergency visits due to Covid by 50 percent and of hospitalizations by 55 percent. Eventually, the study was published in a different journal in June 2026.
May 29, 2026
Executive Order On Childhood Vaccines Directs HHS to Review and Update U.S. Childhood Vaccine Schedule The White House issues an executive order titled “Realigning United States Core Childhood Vaccine Recommendations with Best Practices from Peer, Developed Countries” that instructs federal agencies, including HHS, that the childhood vaccine schedule “should be aligned with scientific evidence and best practices from peer, developed countries while preserving access to vaccines currently available to Americans.” This follows an earlier memorandum from December 5, 2025 instructing HHS to align the childhood vaccine schedule with that of “peer, developed nations.”
June 18, 2026
FDA Advisory Committee Unanimously Recommends Approval of mRNA Influenza Vaccine The Food and Drug Administration’s (FDA’s) Vaccines and Related Biological Products Advisory Committee (VRBPAC) votes unanimously to recommend approval of Moderna’s mRNA vaccine candidate for older adults. In February of this year FDA had said it would not review Moderna’s application for this vaccine, but several weeks later reversed course and agreed to review after Moderna proposed a revised approach to regulatory review. The FDA reports it is likely to make its decision on this vaccine by August 5 this year.
June 30, 2026
Secretary Kennedy Terminates COVID-19 Emergency Use Authorization Declarations for Drugs, Biological Products, and Medical Devices HHS announces Secretary Kennedy has terminated COVID-19 Emergency Use Authorization (EUA) declarations for drugs and biological products and for medical devices after determining these authorizations are no longer needed. The declaration for drugs and biological products will terminate 12 months after the Secretary’s determination, while the declarations for medical devices will terminate 180 days after the Secretary’s determination. EUAs for COVID-19 vaccines had already been terminated.
August 10, 2026
Executive Order on Vaccines Instructs HHS and States to Realign Childhood Vaccine Recommendations The White House releases a new Executive Order (EO) titled “Delivering Gold Standard Childhood Vaccine Recommendations for Americans” that states U.S. childhood vaccine recommendations should be “aligned with scientific evidence and best practices from peer, developed countries,” and sets out three categories of recommended immunization (echoing the January 5 HHS memo described above that issued a new federal childhood vaccine schedule, which has been put on hold by a federal judge). The new EO also directs the HHS Secretary to offer some childhood vaccines such as measles, mumps, and rubella (MMR) as “single vaccines rather than combination products,” and to align vaccine recommendations with findings to be released by a federal panel known as the “HHS Task Force on Safer Childhood Vaccines.”
September 17, 2026
HHS Secretary Names Eight New Members of the U.S. Preventive Services Task Force Secretary of HHS Robert F. Kennedy Jr. names eight new members of the U.S. Preventive Services Task Force (USPSTF), a panel of experts with responsibilities to assess evidence and make recommendations regarding many preventive medical services. The panel has not been convened since March 2025.
September 14, 2026
HHS Institutes New Approach to Counting Deaths in Official CDC Measles Tally Following a public dispute between Governor of Pennsylvania Josh Shapiro and HHS Secretary Robert F. Kennedy, Jr. regarding deaths in the state attributable to measles, HHS states it will take new approach for counting deaths in official CDC statistics about the current measles epidemic in the U.S. Instead of relying on state and local health departments’ reports of measles deaths as was done previously, HHS will now review each each reported case and look to mortality reports and death records collected and analyzed via the National Center for Health Statistics (NCHS). On its measles page, CDC now includes a note saying “CDC will update its reporting [of the number of measles deaths] as additional information becomes available and relevant reviews are completed.” As of October 12, 2026 the state of Pennsylvania has reported six total measles-associated deaths while the CDC page counts two measles deaths only.
October 8, 2026
HHS Launches Agency-Wide Actions Focused on Vaccine Injuries In an announcement, HHS states it is launching a number of actions across the agency focused on vaccine injuries intended “to strengthen how the federal government identifies, documents, investigates, and responds to health problems reported following vaccination.” These actions include opening a new clinic located at NIH “dedicated to studying and caring for patients experiencing health problems following vaccination,” issuing a new proposal to reimburse physicians “for the time they spend submitting reports of suspected vaccine-related injuries to VAERS [the Vaccine Adverse Events Reporting System],” and modernizing VAERS through making the system accessible on mobile devices and improving tools for research using VAERS data.