A Closer Look at State Directed Payments for Nursing Home Services

Published: Oct 21, 2026

The 2025 reconciliation law included major eligibility and financing changes to Medicaid, and at the time of enactment, the Congressional Budget Office (CBO) estimated a reduction in federal Medicaid spending of $911 billion from 2025 through 2034. Some of the reductions stem from new restrictions on Medicaid state directed payments (SDPs) for hospital, nursing home, and other health care services. While states are generally prohibited from directing how managed care organizations (MCOs) pay for care, states can implement SDPs that require MCOs to increase rates or set minimum rates for specified Medicaid services. In authorizing SDPs, the Centers for Medicare and Medicaid Services (CMS) aimed to help states improve access to care and provider participation. Many states that contract with MCOs use SDPs to make uniform rate increases that function like supplemental payments in fee-for-service (FFS) Medicaid. Building on previous analysis of SDPs, this issue brief takes a closer look at SDPs for nursing home services.

The analysis includes 20 preprints from 15 states, from SDPs that were publicly available and approved from January 1, 2024 through May 12, 2026. Preprints are application forms submitted to the federal government that document how states direct Medicaid managed care plans to pay providers using SDPs. Preprints are the only national source of data on SDPs but are limited because there are gaps in data provided by the preprints (see Methods for more details). Other preprints for nursing home services may have been approved since May 12, 2026. Key takeaways include:

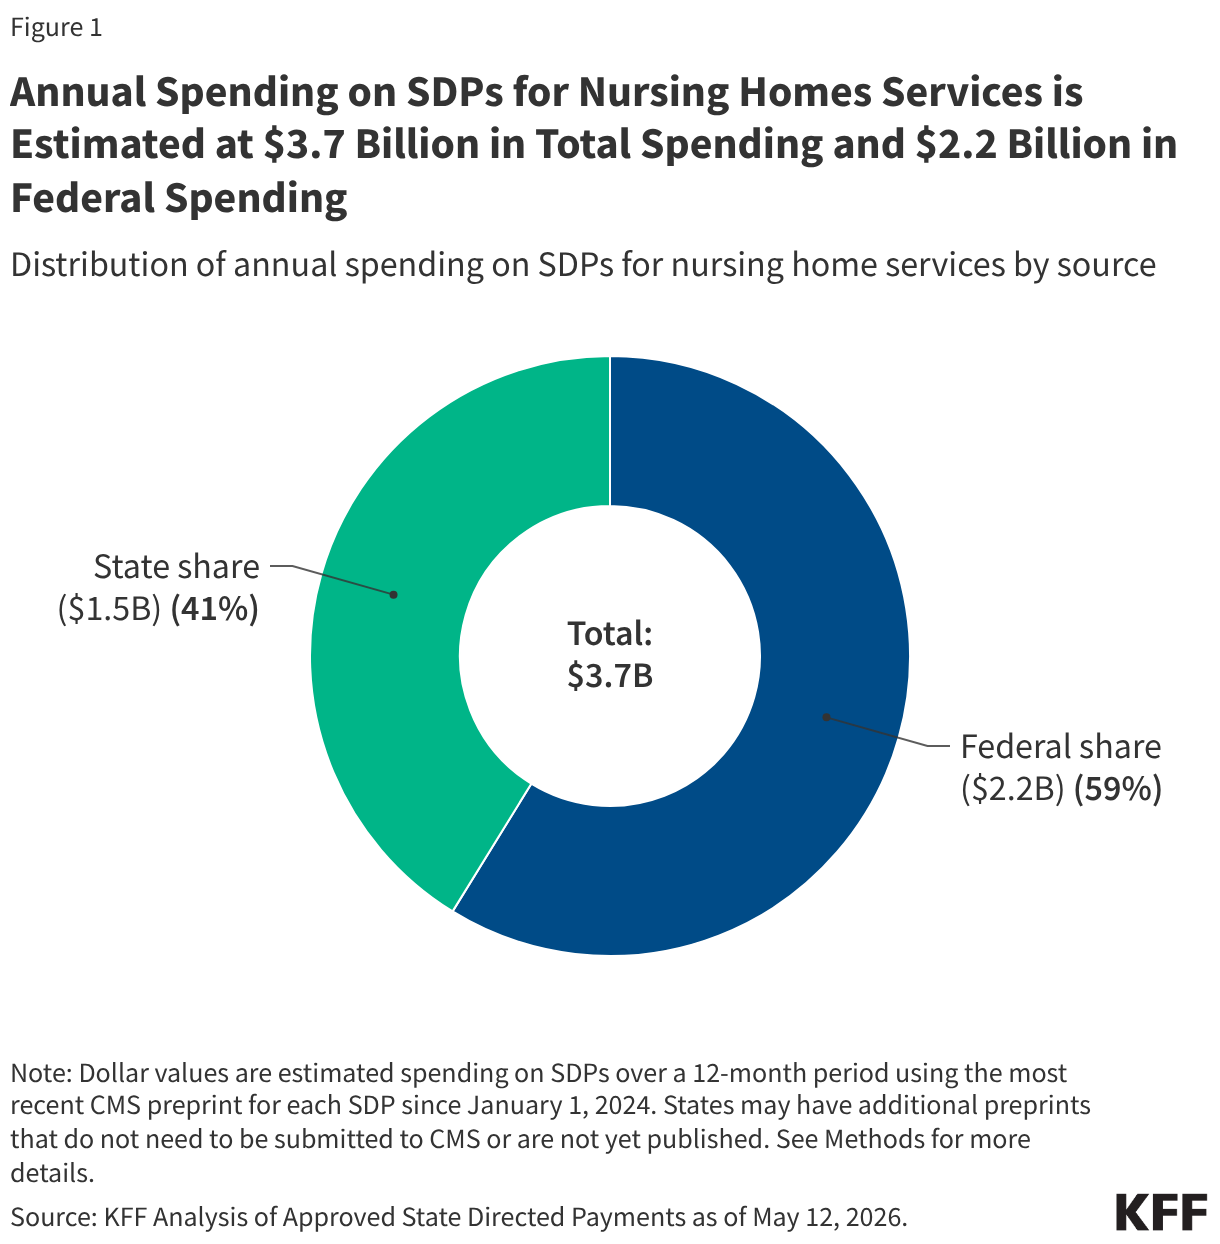
  • Annual spending on SDPs for nursing home services is estimated at $3.7 billion in total spending and $2.2 billion in federal spending, which is about three percent of total SDP spending and two percent of total federal SDP spending.
  • At least 15 states have SDPs that pay for nursing home services, and many of those payments could be reduced under new limits for SDPs from the 2025 reconciliation law.
  • Much remains unknown about how forthcoming policy changes for SDPs will affect states, nursing homes, and nursing home residents (two-thirds of whom have Medicaid as a primary payer), but data about existing SDPs highlight states and services for which changes could be most substantial.

Annual spending on state directed payments (SDPs) for nursing home services is estimated at $3.7 billion in total spending and $2.2 billion in federal spending (Figure 1). This is only about 2% of total federal SDP spending, with most (84%) federal SDP spending directed to hospital services. Based on states’ projected spending in the preprints, the federal government pays an estimated 60% of total spending on SDPs for nursing home services, and the remainder is paid through the state share of SDP financing. The federal and state shares of financing are determined using the standard formulas for Medicaid financing and reflect the state’s federal matching assistance percentage. The state share of financing may come from a variety of sources including state general fund revenues, provider taxes, and intergovernmental transfers. Among the 15 states with SDPs for nursing home services, 11 finance part or all of the state share with provider taxes and 4 states finance part or all of the state share with Intergovernmental transfers.

Federal spending on SDPs for nursing home services ($2.2 billion) accounts for 2.4% of total federal spending on SDPs. Federal spending on SDPs is expected to decrease in future years because of new limits established by the 2025 reconciliation law. Under the limits, the total payment amount under the SDP may not exceed 100% of the Medicare payment rate in states that have adopted the Affordable Care Act (ACA) Medicaid expansion (“expansion states”) and 110% of the Medicare payment rate for non-expansion states. Payment rates for services without an applicable Medicare payment rate are limited to Medicaid fee-for-service rates. Certain SDPs are initially grandfathered (i.e., allowed to continue), but total spending amounts will be reduced by 10 percentage points each year (starting January 1, 2028) until they reach the allowable Medicare-related payment limit. 

Annual Spending on SDPs for Nursing Homes Services is Estimated at .7 Billion in Total Spending and .2 Billion in Federal Spending (Donut Chart)

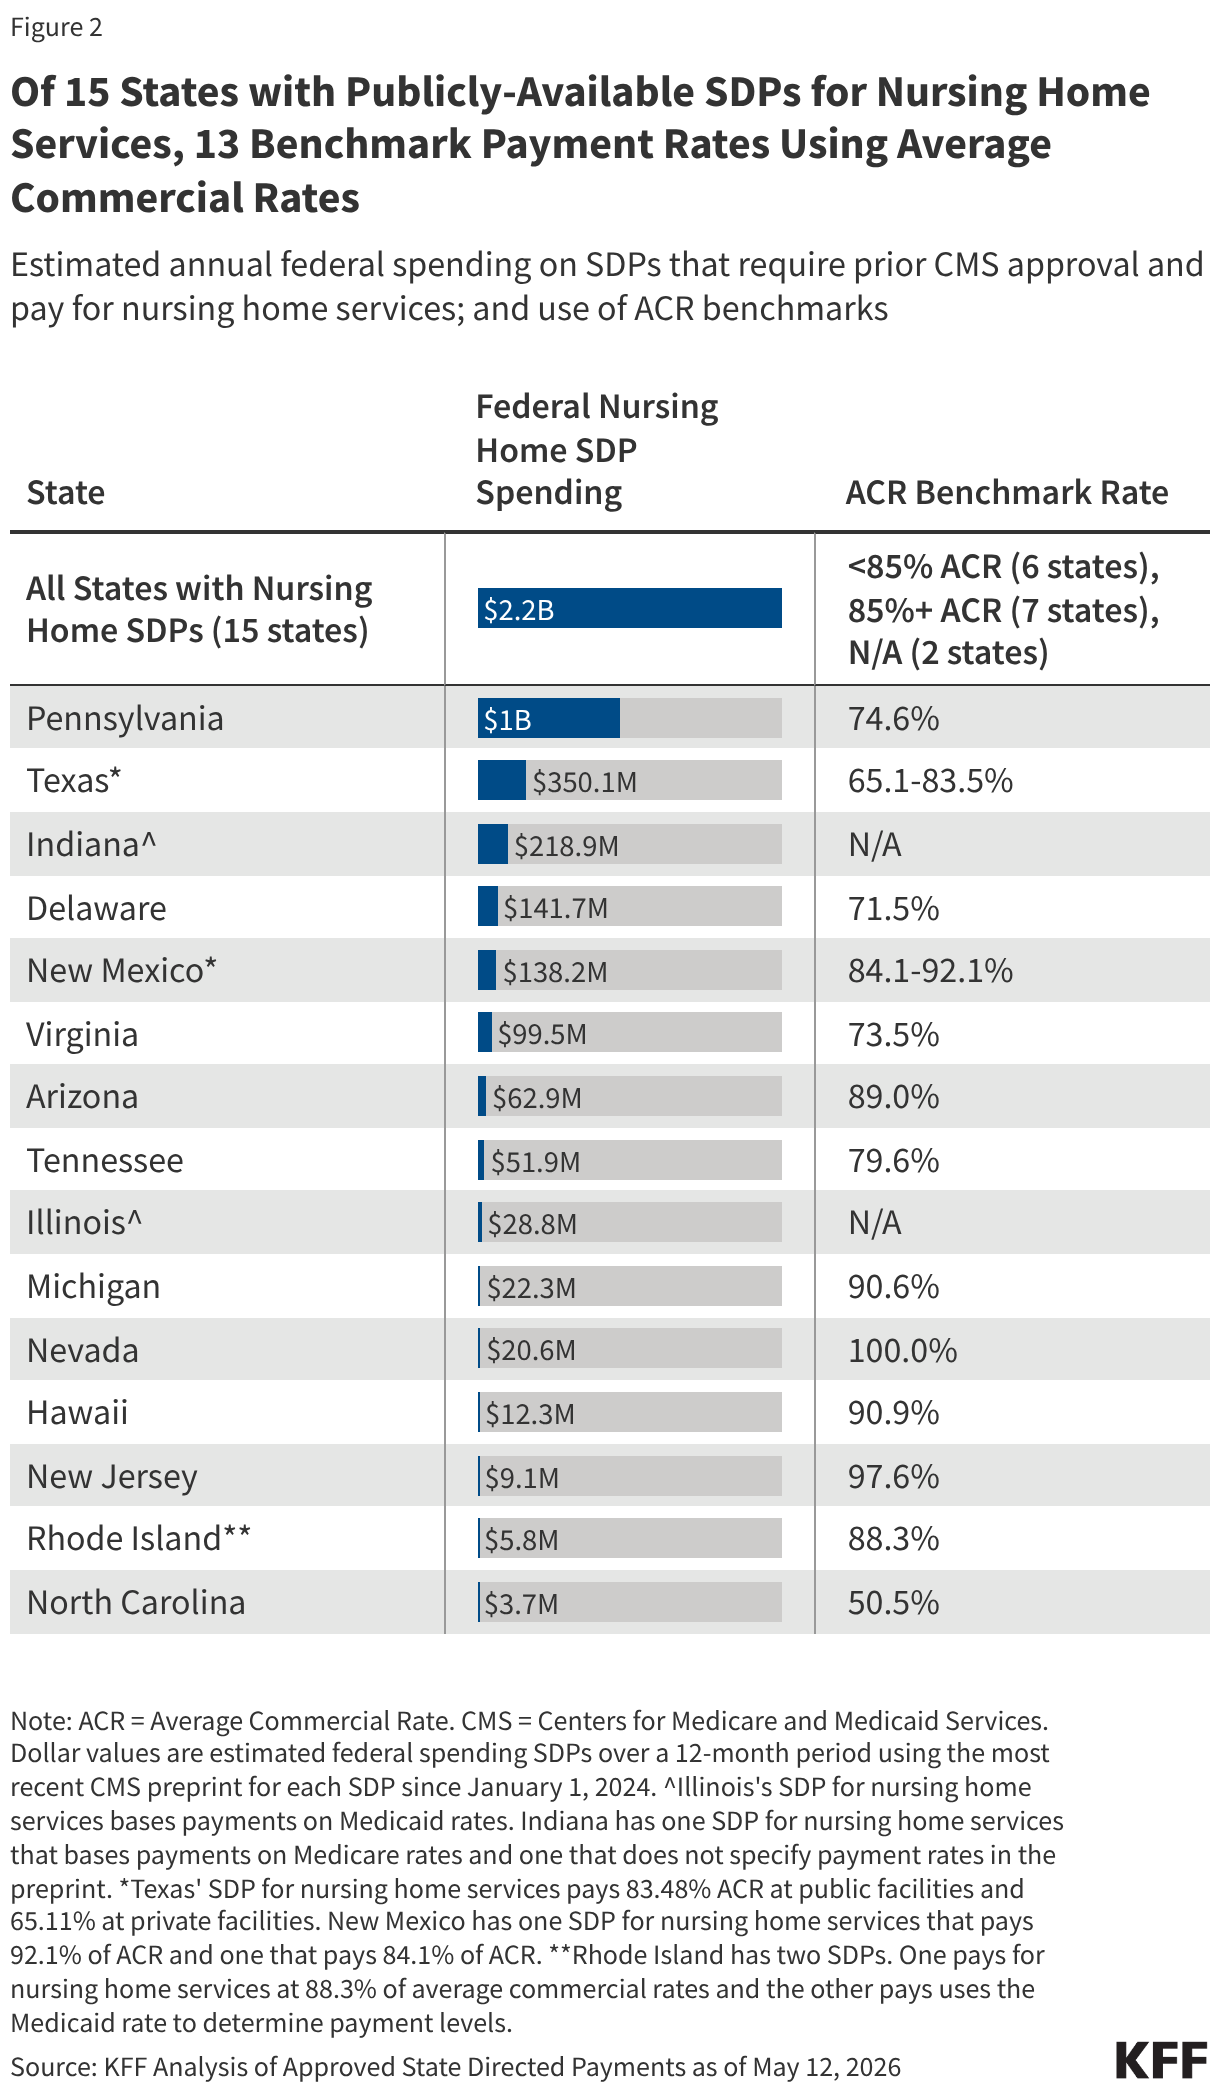
Of the 15 states with publicly available SDPs for nursing home services, 13 benchmark payment rates using average commercial rates (Figure 2). Among these 13 states, 12 states exclusively use average commercial rates when establishing SDP payment rates for nursing home services. Pennsylvania accounts for nearly half (47%) of the $2.2 billion in federal spending on SDPs for nursing home services and sets payment rates at 74.6% of average commercial rates. Rhode Island has two SDPs for nursing home services: One pays for nursing home services at 88.3% of average commercial rates, and the other uses the Medicaid rate to determine payment levels. Indiana and Illinois do not use the average commercial rate to benchmark any of their SDPs for nursing home services. Illinois benchmarks its SDP for nursing home services to Medicaid rates. Indiana benchmarks one SDP for nursing home services to Medicare and does not specify a benchmark in the other SDP.

Of 15 States with Publicly-Available SDPs for Nursing Home Services, 13 Benchmark Payment Rates Using Average Commercial Rates (Table)

It is unclear how much payment rates will have to decrease to come into compliance with the new payment limits established in the 2025 reconciliation law. For other types of services, research shows that average commercial rates are higher than Medicare rates, particularly in the case of hospital services and physician services. However, there are not similar data or studies available to estimate how average commercial rates for nursing homes compare with Medicare or Medicaid rates, making it more difficult to anticipate how the changes in law could affect nursing home payment rates nationally. States may have additional data internally, but those are not publicly available, and variation across states could be considerable.

In its regulatory analysis of the proposed regulation on SDPs, CMS assumed that Medicaid payment rates were 80% of Medicare rates for nursing home services and that average commercial rates were 150% of Medicare rates, but also highlighted uncertainty. CMS writes that “there is little information on nursing [home] prices and the services that Medicare covers may be significantly different than those covered by private payers and Medicaid.” CMS’s finding is consistent with data from a 2023 Medicaid and CHIP Payment and Access Commission (MACPAC) analysis of Medicaid nursing home payment rates relative to Medicare payment rates and costs. The analysis found that Medicaid base payment rates (not accounting for supplemental payments) varied considerably but were generally lower than those of Medicare. However, MACPAC reported that Medicaid and Medicare rates were not comparable because of differences in residents’ level of need. The proposed regulation specifies that the skilled nursing facility prospective payment system will define Medicare payment rates for nursing facility services, but it is unclear how that per diem payment rate will translate into the limits on SDPs for nursing home services.

Nursing homes will likely vary in how they are impacted by lower SDP spending, and it is unknown how the new limits will affect access to care among Medicaid enrollees who use nursing home services. The effects for specific nursing homes will depend on how much they are currently receiving in SDPs, how much their revenues decline as the new limits take effect, and how dependent they are on SDP revenues. Effects will vary across states but also within states because states may direct SDPs to a subset of nursing homes, or sometimes a single nursing home, and among eligible nursing homes, SDPs vary with Medicaid patient volume. Nursing homes’ abilities to absorb reduced payment rates also varies. For nursing homes with relatively high operating margins, changes to SDP revenues might be more easily absorbed. On the other hand, nursing homes with relatively low operating margins may adapt in ways that affect Medicaid enrollees’ access to care, such as reducing the number of Medicaid beds available or closing.

This work was supported in part by Arnold Ventures and The John A. Hartford Foundation. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.

Methods

Data source: This analysis uses data available from the list of approved state directed payment preprints published by the Centers for Medicare and Medicaid Services (CMS) as of May 12, 2026. The approved state directed payment (SDP) preprints are PDF versions of forms that are completed by states and approved by CMS. States are required to seek approval using such a preprint for any SDP that requires managed care organizations (MCOs) to pay for services at any rate other than fee-for-service (FFS) Medicare or Medicaid rates. The approved preprints are often posted online 6–12 months after their start date, although some approved preprints are posted online much later.

KFF developed a Python script to download the available PDFs, extract relevant data from them, and standardize certain fields. Each preprint was turned into one row in a spreadsheet. Data from tables within the preprint were extracted and converted into separate tables in KFF’s data file with each row in the preprint table converted into a row in the spreadsheet table.

SDP preprint inclusion criteria: KFF included all SDPs in the analysis with a rating period start date of January 1, 2024 onwards for the 50 states and Washington DC (hereafter referred to as a state). Puerto Rico was the only territory that had published SDPs, which were excluded. In each case, KFF only kept the most recent preprint for any given SDP. For example, if an SDP had an initial approval in 2024 and then renewals in 2025 and 2026, KFF would only include the 2026 renewal in the final dataset. Out of the 305 preprints included in this analysis, 24 (totaling $8.8 billion in federal spending) ended in calendar year 2024.

A small number of SDP preprints were excluded due to file formatting or data validity issues. Specifically:

  • Data from five preprints were encoded differently, so the data could not be programmatically extracted into the dataset and were therefore excluded from the analysis (two from New Hampshire, one from Ohio, and two from Florida, totaling $89 million in federal spending for one year).
  • Data from preprints that had obvious data quality issues were excluded from this sample. For instance, two were from Illinois (which projected total annual spending of more than $100 billion) while one from Minnesota did not report spending data in the preprint.

KFF also reviewed all preprints with end dates prior to July 1, 2025, and excluded preprints for the following reasons:

  • The preprint was likely funded from COVID-19 relief dollars (including the increased federal funding for home care from the American Rescue Plan Act) and so was unlikely to still be in place.
  • The preprint was likely combined into a different preprint when renewed or was otherwise renamed when renewed.
  • The preprint ended in 2024, and online research suggests that the payment was discontinued.

See Table 1 for a list of the inclusion criteria, the counts of preprints after each criterion was applied, and the federal spending for preprints that were retained at each stage.

Calculating total spending on SDPs: This analysis used the states’ projected total, federal, and state spending from the preprint. Most preprints are for a one-year period, but some are for longer or shorter periods. In such cases, KFF adjusted the data to be a one-year equivalent. When preprints were for periods shorter than 12 months, dollars were scaled up (e.g., if the preprint was for 6 months, the spending was multiplied by two) and for preprints that were for periods longer than 12 months, spending was scaled down (e.g., retaining two-thirds of spending if the preprint extended for 18 months).

KFF also manually reviewed the federal spending numbers because some states reported them as percentages and others reported them as dollar amounts. Manual review ensured the Python script had adequately handled the different reporting structures.

Calculating SDP spending by service type: For preprints that made payments for multiple service types (which accounted for $32.6 billion in federal spending), spending was apportioned across service types.

  • For SDPs directed to hospital and non-hospital services, 90% of spending was allocated to hospital services. Remaining dollars were apportioned equally among any other service types.
  • For SDPs directed to both inpatient and outpatient hospital services, 68% of hospital spending was allocated to inpatient services and 32% was allocated to outpatient services. This assumption does not affect the estimates of spending by service type but is relevant for calculating the amount of spending by benchmark rate.
  • For SDPs that did not direct any spending to hospital services, spending was allocated equally among named services.

Apportioning spending across service types is difficult, and KFF used a variety of sources to approach developing the most realistic assumptions feasible. KFF analyzed data on Medicaid spending including CMS-64 spending by service type, data on Medicaid spending by service type from the National Health Expenditures, the Congressional Budget Office Medicaid baseline, and existing studies on hospital payment policies such as those from the Medicaid and CHIP Payment and Access Commission (MACPAC). All of those data points suggest that the vast majority of SDP spending pays for hospital services, and $53.1 billion of the $60.5 billion in federal spending from preprints directed to a single provider type went to hospital services. KFF also strove to use an assumption that resulted in estimates of hospital SDP spending that are similar to what could be expected on the basis of other data and research as described above.

When identifying the service types in the preprints, the Python script attempted to align service types between preprint Table 2 (which specifies payment rates for sets of providers) and preprint Question 20 (a checklist of services included in the SDP). In many cases, this alignment involved some uncertainty, requiring manual review and classification of service types.

Identifying benchmarks for MCO payments: The most common type of SDP requires MCOs to make payments that are on top of the regular base payment rate (as opposed to limiting or replacing the negotiated rate). In such cases, payments are measured using a “benchmark” or standardized rate to compare the MCO rates to other payment rates such as those of Medicaid FFS, Medicare FFS, or the average among commercial payers (“average commercial rates”). Among the 305 preprints in this sample (accounting for $93.1 billion in federal spending), 264 preprints are required to report a benchmark (accounting for $87.9 billion in federal spending). KFF used the Python script to identify the applicable benchmark type from the preprint, but also manually reviewed the data since states sometimes used inconsistent terminology to report the same benchmarks.

Identifying payment levels: To identify how current payment rates align with the new limits on SDPs in the reconciliation law, KFF first needed to identify payment levels in the preprints. The level is specified as a percentage of the benchmark (e.g., 90% of average commercial rates or 140% of Medicare rates). Both types of payments were pulled from Table 2 when available. Payment rates for inpatient and outpatient hospital services were tracked separately with each row in Table 2 when applicable.

SDPs for nursing facility services: KFF further limited the sample of SDPs to only those that specified nursing facility services as a service type in Question 20.


Methods Table 1

Analysis StepCount of PreprintsFederal Spending Among Preprints (billion $)Notes
Preprints listed on CMS’s website as of May 12, 20261,038


All preprints pulled from CMS website987246.4Some links are broken or duplicates
Preprints in time period and states570 
166.1
 
Includes the most recent preprint for each state directed payment (SDP) from January 2024 onwards for the 50 states and DC
Most recent SDP submission or renewal35899.6


Preprints without data quality issues35299.6KFF dropped preprints that were missing information about the start date, end date, spending amounts, etc.
Preprints manually reviewed and dropped30593.1KFF dropped preprints from older years that were subsumed into newer preprints and those that were temporary policies started during the COVID-19 pandemic
Include nursing home services202.2


KFF Health Information and Trust Polling Dashboard

Key insights and trends from KFF’s polling on Health Information and Trust

Last Updated:

October 20, 2026

Trusted Sources of Health Information

Who the Public Trusts For Health Information

Copy link to Who the Public Trusts For Health Information

Doctors and other health care providers are the public’s most trusted source of health information, while trust in government health agencies and officials is much more divided. A large majority of adults express at least “a fair amount” of trust in their doctor for reliable information about health issues, while half say they trust the CDC or FDA and fewer than half express trust in their state government officials, HHS Secretary Robert F. Kennedy, Jr., or President Trump.

Partisanship shapes who the public trusts for health information, especially when it comes to Secretary Kennedy and President Trump. Roughly six in ten Republicans, rising to at least seven in ten among MAGA-supporting Republicans, say they trust Secretary Kennedy or President Trump for reliable health information compared to three in ten or fewer independents and Democrats who say the same. On the other hand, Democrats are more likely than Republicans to trust their state officials for health information, while similar shares of Democrats and Republicans say they trust the CDC or FDA. Individual health care providers are the most-trusted source for health information across partisanship.

Across demographic groups – including age, gender, race and ethnicity, and education – health care providers remain the most trusted source of health information. For other health information sources, trust can vary by different groups. White adults and those with a college degree are more likely to express trust in their doctor or health care provider, which may reflect health care access issues. Trust in the CDC and state government officials also differs by education, with college-educated adults more likely to express trust in these sources. White adults are more likely than their peers to express trust in Secretary Kennedy and President Trump for health information.

Confidence in Federal Health Agencies

Copy link to Confidence in Federal Health Agencies

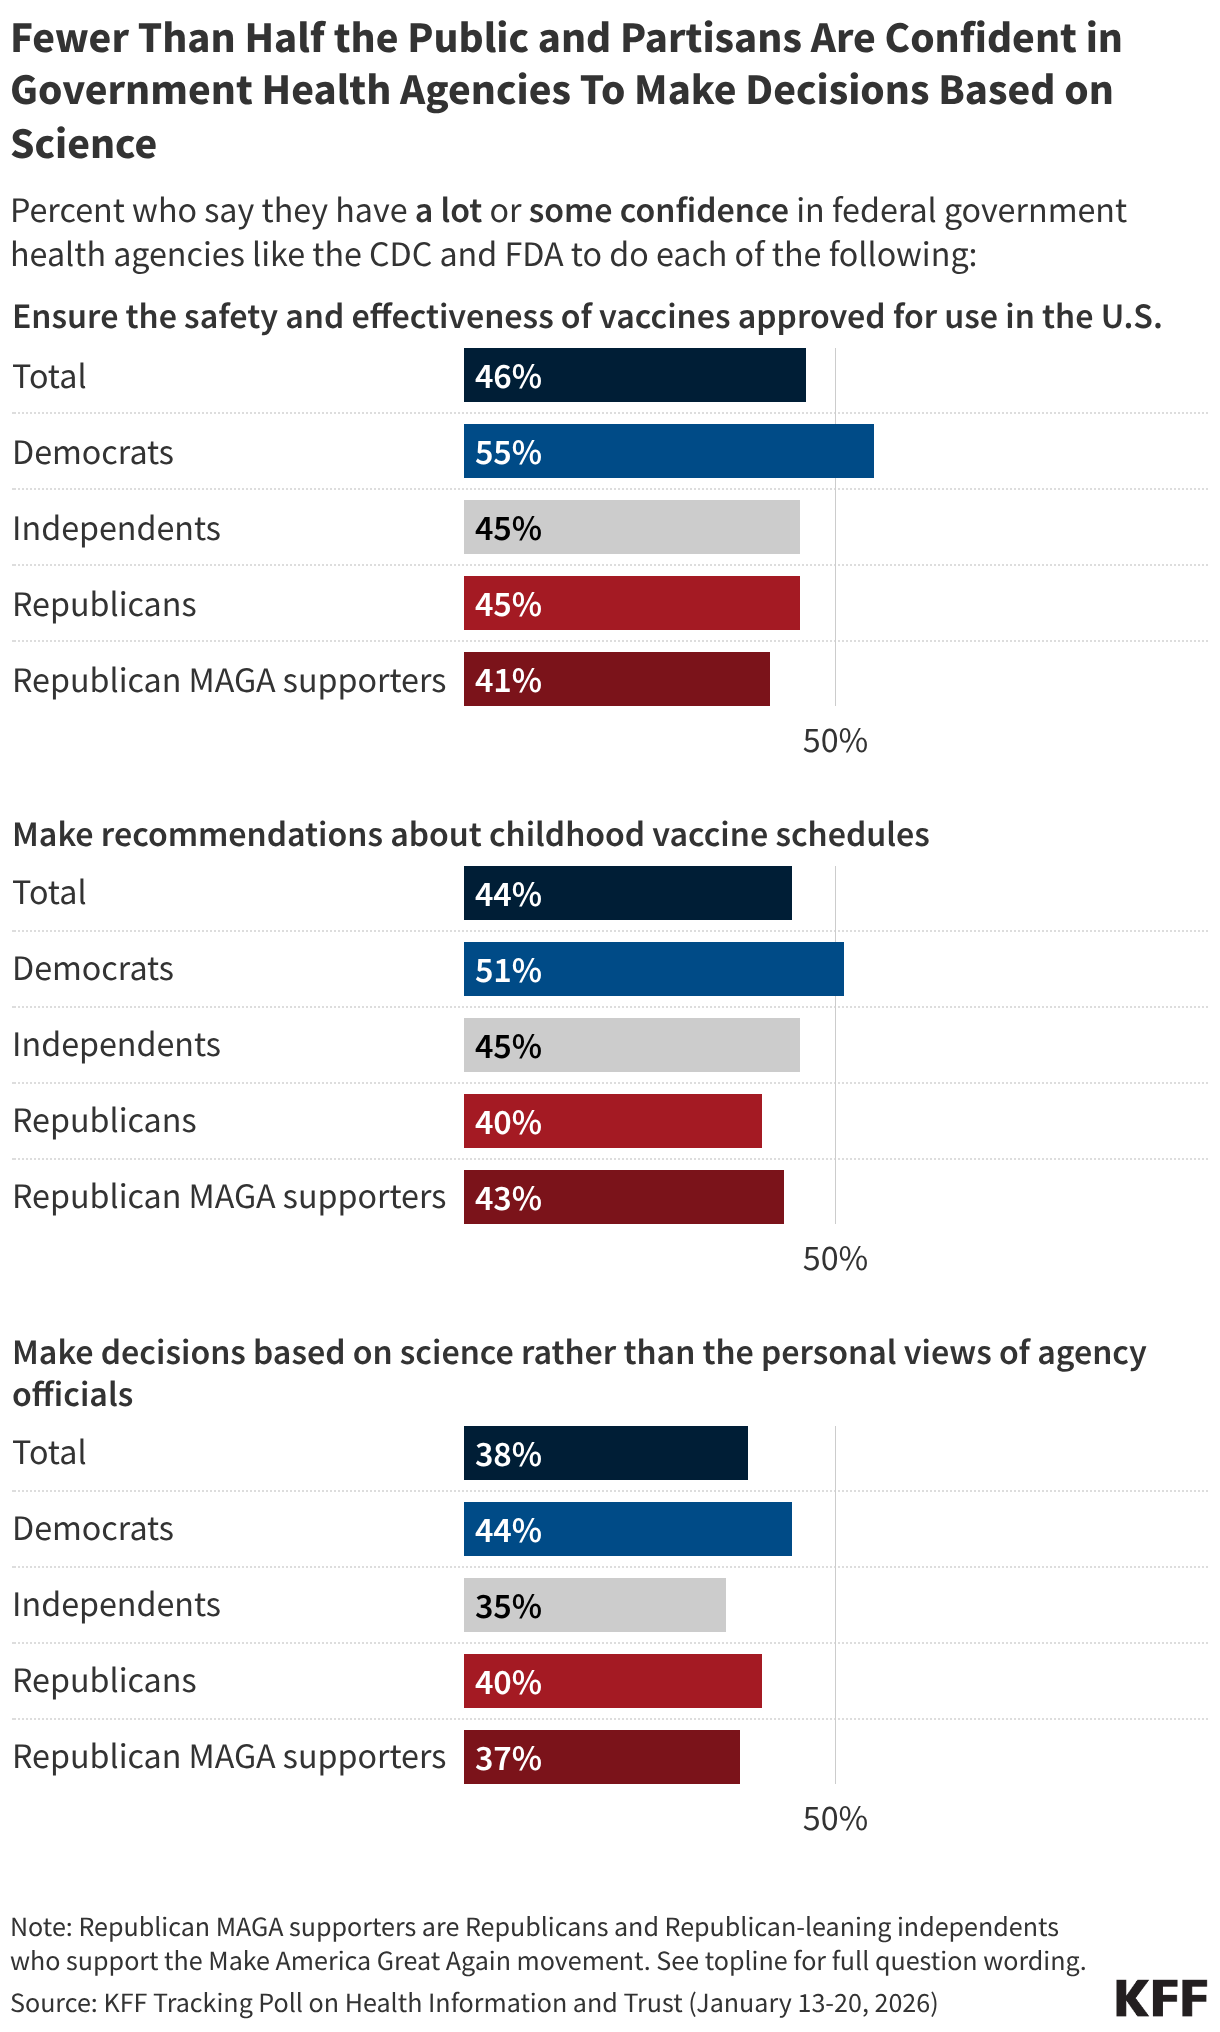
Most of the public lacks confidence in agencies like the CDC or FDA to carry out many of their core responsibilities. While Democrats are somewhat more likely than Republicans to have at least “some confidence” in government health agencies to ensure vaccine safety and effectiveness and make recommendations about the childhood vaccine schedule, fewer than half across partisans have confidence in these agencies to make decisions based on science. For more information, see KFF’s January 2026 Tracking Poll on Health Information and Trust.

Fewer Than Half the Public and Partisans Are Confident in Government Health Agencies To Make Decisions Based on Science (Bar Chart)

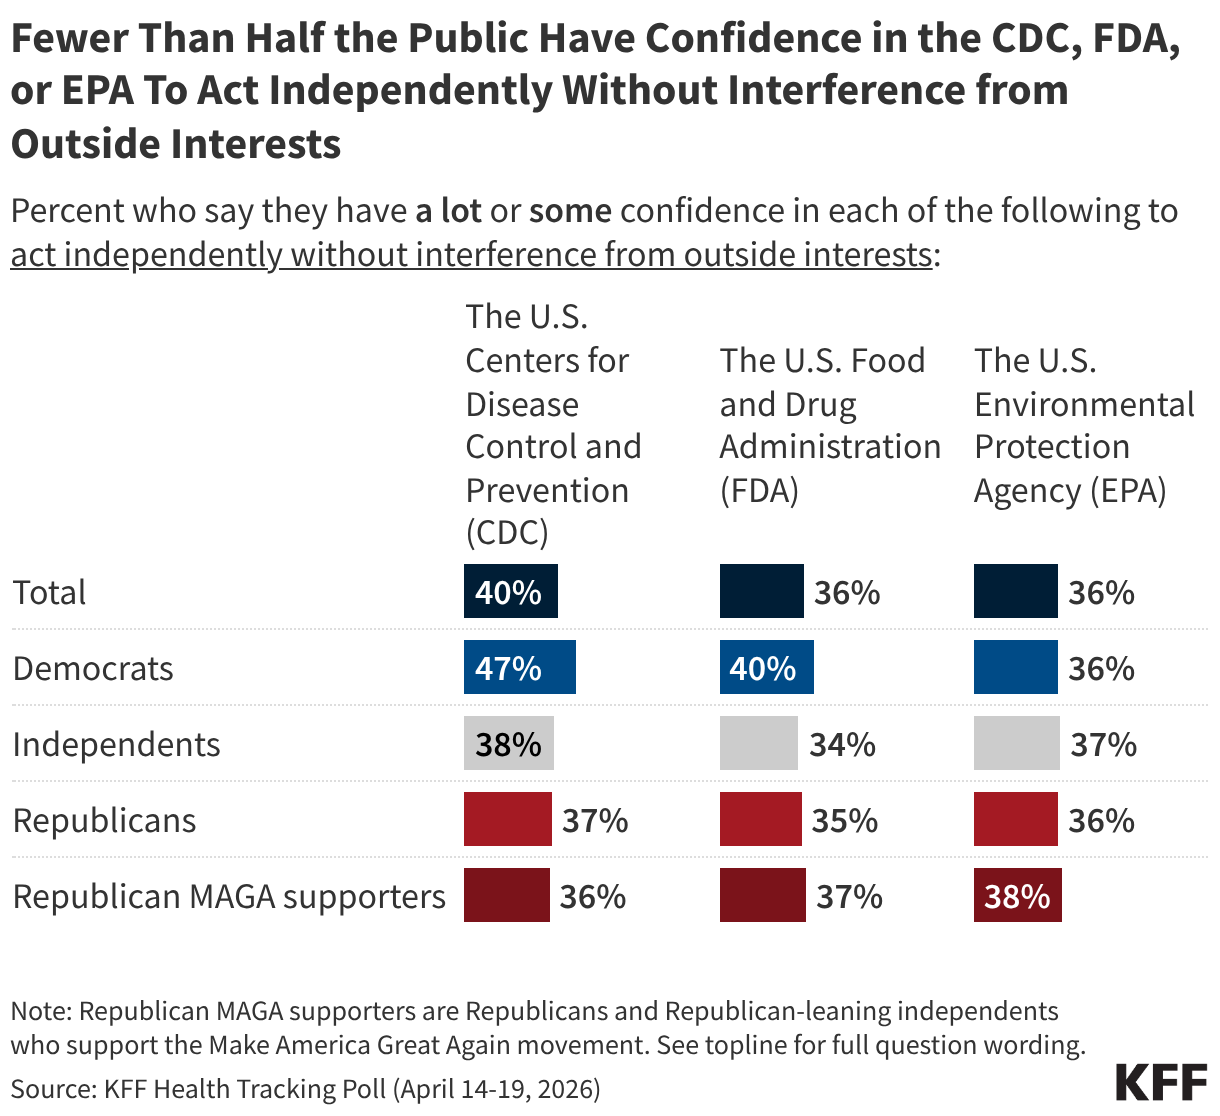
Less than half of the public and partisans express at least “some confidence” in the CDC, FDA, or EPA to act independently without outside interference. Democrats are somewhat more likely to say they have confidence in the CDC to act independently, with almost half expressing confidence. On the other hand, four in ten or fewer adults and partisans express confidence in the independence of the FDA or the EPA. For more information, see KFF’s April 2026 Health Tracking Poll.

Fewer Than Half the Public Have Confidence in the CDC, FDA, or EPA To Act Independently Without Interference from Outside Interests (Split Bars)

Trends in Trust of Government Health Agencies and Officials

Copy link to Trends in Trust of Government Health Agencies and Officials

At the onset of the COVID-19 pandemic, there were high levels of bipartisan trust in information about the new virus from the U.S. Centers for Disease Control and Prevention (CDC). Trust in the agency for information about COVID-19 vaccines, and vaccines more generally, subsequently declined amid widening partisan divisions and large drops in Republican trust. Democratic trust in the agency has since declined significantly following President Trump’s reelection and the confirmation of Robert F. Kennedy Jr. as HHS Secretary. Amid these partisan shifts, half of the public now express trust in the CDC for reliable vaccine information. Keep scrolling to see trends among the public and partisans.  

KFF polling has found trust in vaccine information from other health agencies and officials has also declined amid partisan divisions since 2020, including for the U.S. Food and Drug Administration (FDA), state government officials, and local public health departments. 

Who Parents Trust for Childhood Vaccine Information

Copy link to Who Parents Trust for Childhood Vaccine Information

Among parents of children under age 18, pediatricians are the most trusted source of reliable vaccine information. Smaller shares, but still majorities, also trust their local public health department, the CDC, and the FDA. Over half of parents trust their friends and family for vaccine information, while far fewer express trust in Robert F. Kennedy Jr., pharmaceutical companies, or health and wellness influencers. As with the public overall, partisanship plays a role in who parents trust for vaccine information. For more information, see the KFF/Washington Post Survey of Parents.

Among parents, Secretary Kennedy garners trust on vaccines from a majority of Republican supporters of the Make America Great Again, or MAGA, movement (18% of all parents) and supporters of the Make America Healthy Again, or MAHA, movement (38% of all parents). While slim majorities of these MAGA and MAHA parents trust Kennedy for vaccine information, larger shares express trust in their child’s pediatrician.

Social Media and AI

Social Media Use for Health Information

Copy link to Social Media Use for Health Information

About three in ten adults say they use social media to find health information and advice “at least monthly,” including larger shares of younger adults, Black and Hispanic adults, lower income adults, and those with lower educational attainment. For more information see KFF’s June 2026 Tracking Poll on Health Information and Trust.

Stacked bar chart showing how often U.S. adults report using social media. Results shown by age gender, race/ethnicity, and party ID.

About one-third of adults who use social media for health information say a “major reason” they turned to social media for health advice was because they wanted to learn from people with similar experiences or because they wanted immediate information or support. About one in six users cite difficulty accessing or affording health care as a major reason.  

Learning From People Who Share Similar Health Experiences Is a Top Reason Adults Use Social Media for Health Information and Advice (Stacked Bars)

Similar shares of adults who use social media for health information or use AI chatbots for health information cite difficulties accessing or affording health care as major reasons they turned to these tools for health advice. These reasons are more commonly cited among lower income social media and AI users. For additional information on use of AI for health information, see AI and Health Information section below.

Similar Shares of Adults Who Use Social Media or AI for Health Information Say Not Having a Regular Provider Was a Reason for Using These Tools (Stacked Bars)
Among Adults Who Use Social Media or AI For Health Information, Those With Lower Incomes Are More Likely To Cite Access and Affordability Issues as a Major Reason (Split Bars)

While fewer than half of the public report actively using social media at least monthly to find health information and advice, larger shares report being exposed to such information in the past month, with majorities saying they have recently seen content related to weight loss, diet, or nutrition and mental health.

While four in ten social media users say they regularly get information about news and politics from social media influencers, far fewer (15%) say they turn to influencers for health information and advice. Younger adults, Black adults, and more frequent social media users are more likely than their peers to say they rely on influencers for health information. For more information on the relative impact of influencers on the public and health policy debates, see KFF CEO Drew Altman’s column.

Split bar chart showing the share of U.S. adults who report regularly getting health information and advice and news about politics from influencers on social media. Results by age gender, party ID, and social media use.

Trust in Social Media for Health Information

Copy link to Trust in Social Media for Health Information

Across different social media platforms, fewer than half of users say they find at least “some” of the health information they see on these platforms to be trustworthy. Younger users tend to be more trusting than older users of health content on certain platforms including TikTok, YouTube, Instagram, and Reddit.

AI and Health Information

Copy link to AI and Health Information

About a third (32%) of the public reports turning to AI chatbots for health information and advice in the past year – rivaling social media as a health information source, but less common than reliance on health care providers or internet search engines (where they may be encountering AI generated results, even if they are not looking for them). The share of adults using AI for health information includes three in ten who say they’ve used these chatbots in the past year for information or advice about their physical health, and one in six who’ve used them for mental health information or advice. For more information, see KFF’s March 2026 Tracking Poll on Health Information and Trust.

Split bar chart showing percent who have sought information or advice about their physical or mental health from specific sources in the past year.

Larger shares of younger adults report turning to AI for either physical health or mental health information in the past year. When it comes to mental health advice, uninsured adults and Black and Hispanic adults are more likely than insured adults and White adults to have turned to AI.

People report using AI for either physical health or mental health information in a variety of ways, most commonly to look up symptoms or general information about health conditions. Fewer say they used AI to help make decisions about whether to seek medical care for either physical or mental health concerns.

Bar chart showing percent who say they have used artificial intelligence tools for information and advice about their physical health in the past year, and whether they have used it for specific reasons.

The most common reason people cite for turning to AI for health advice is wanting quick or immediate support. Many also cite wanting to look up information before seeing a provider or feeling more comfortable looking up health questions privately. One in five cite health care access or affordability issues as major reasons for turning to AI for health questions, including larger shares of younger adults and those with lower household incomes

Among the public overall, few adults say they trust AI tools to provide reliable information about health, but most adults who have used AI for health information and advice say they trust these chatbots to provide reliable health information.

Split bar chart showing trust in AI tools to provide reliable information about health and mental health respectively. Results shown by total adults and by use of AI for different types of health information.

False or Unproven Health Claims

Awareness and Belief in False or Unproven Health Claims

Copy link to Awareness and Belief in False or Unproven Health Claims

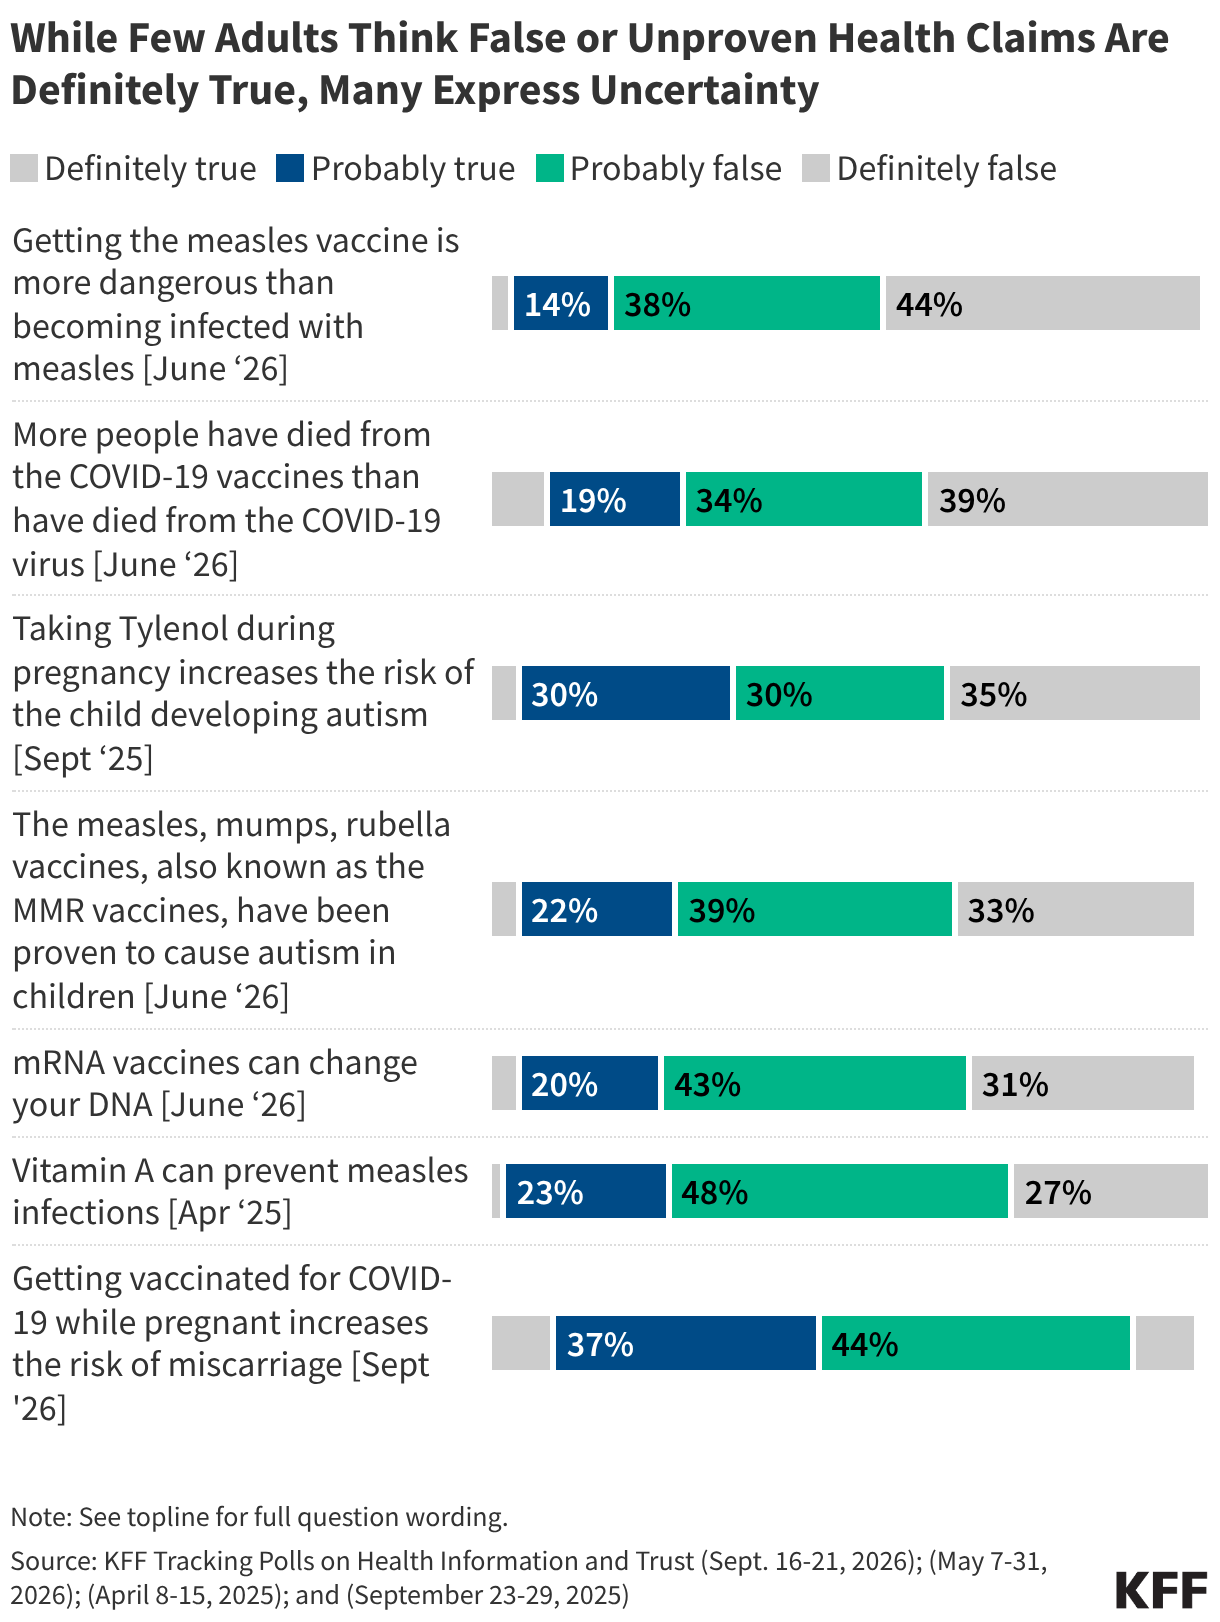
Exposure to health misinformation is often widespread, but relatively small shares of the public express certainty that many false or unproven claims are true. In fact, at least half of the public fall in a “malleable middle,” saying these claims are either “probably true” or “probably false.” The public’s uncertainty around false or unproven health claims related to COVID-19 , vaccines , measles  and the purported causal link between Tylenol and autism presents an opportunity for interventions to clear up confusion and deliver accurate information.

Measuring Exposure

Copy link to Measuring Exposure

KFF polls have measured exposure to a wide array of false, misleading, and unproven health claims since 2023. Exposure varies widely depending on the topic and prominence of news coverage of the claim. The most widely heard of those tested in KFF polls is that taking Tylenol during pregnancy increases the risk of a child developing autism, a claim cited by President Trump in a widely covered September 2025 press conference.

The Malleable Middle

Copy link to The Malleable Middle

Across an array of false or unproven health claims measured in KFF surveys, few adults are certain these claims are “definitely true” while much larger shares say they are “definitely false.” For most claims, at least half express uncertainty, falling into the malleable middle and saying the claims are either “probably true” or “probably false.” Seven recent false or unproven health claims measured in 2026 and 2025 KFF surveys are shown below.

While Few Adults Think False or Unproven Health Claims Are Definitely True, Many Express Uncertainty (Stacked Bars)

Typology of Belief Across Vaccine Myths

Copy link to Typology of Belief Across Vaccine Myths

While KFF polling has consistently found that much of the public falls in the “malleable middle” when it comes to a wide array of false health claims, there are nuances within this group that can be examined by looking at patterns of belief across multiple myths. KFF’s June 2026 Tracking Poll on Health Information and Trust identified five groups based off patterns of belief across four common vaccine myths:

KFF polling has measured exposure to and belief in false or unproven claims across a wide array of topics. For information on belief in additional claims about COVID-19, reproductive health, and gun violence, see KFF’s Health Misinformation Tracking Poll Pilot.  For information on additional false claims related to COVID-19, see KFF’s May 2022, and October 2021 COVID-19 Vaccine Monitors.

Belief in False or Unproven Health Claims

Copy link to Belief in False or Unproven Health Claims

KFF polling has found partisanship and education play a substantial role in belief of false or unproven health claims about vaccines, COVID-19 and measles. Republicans and adults without a college degree are consistently more likely than Democrats and college educated adults, respectively, to believe or lean towards believing vaccine-related myths. For more information, see KFF's June 2026 Tracking Poll on Health Information and Trust.

Beyond partisanship and education, belief in common vaccine myths sometimes varies by age and race and ethnicity. Larger shares of adults ages 30-49 compared to older adults say false claims about vaccines are either definitely or probably true, as do Black adults compared to White adults. Hispanic adults are more likely than White adults to endorse two false claims about the measles vaccines. These differences show that susceptibility to health misinformation among some groups can vary depending on the topic, which may reflect different information channels relied upon by these groups (see social media and news sources sections for more information).

Adults who frequently use social media or artificial intelligence (AI) tools for health information are more likely to say several false claims about vaccines are definitely or probably true, as are those who lack a trusted health care provider compared to those who have a provider they trust to answer questions about their health.

Appendix For False or Unproven Health Claims

Copy link to Appendix For False or Unproven Health Claims

KFF polling has sought to examine the public’s exposure to and belief in a wide array of false or unproven health claims. Many of the false or unproven claims measured in KFF surveys have been amplified by or directly made by government officials, while others have been more nebulously shared and spread in public media over the years. Below is a list of sources to document these claims’ inaccuracy.

Table

Vaccine Attitudes

Views on Vaccine Safety Among the Public

Copy link to Views on Vaccine Safety Among the Public

Most U.S. adults, including majorities across partisans, express confidence in the safety of many routine vaccines for children, including MMR, polio, and hepatitis B. Similarly, large majorities of adults ages 50 and over are confident that vaccines for pneumonia and shingles are safe. Views on the safety of COVID-19 and flu vaccines for both adults and children are more divided, with large shares of Democrats expressing confidence compared with smaller shares of Republicans. For more information, see KFF’s, September 2026, January 2026 and April 2025 Tracking Polls on Health Information and Trust.

Parents’ Vaccine Attitudes and Behavior

Copy link to Parents’ Vaccine Attitudes and Behavior

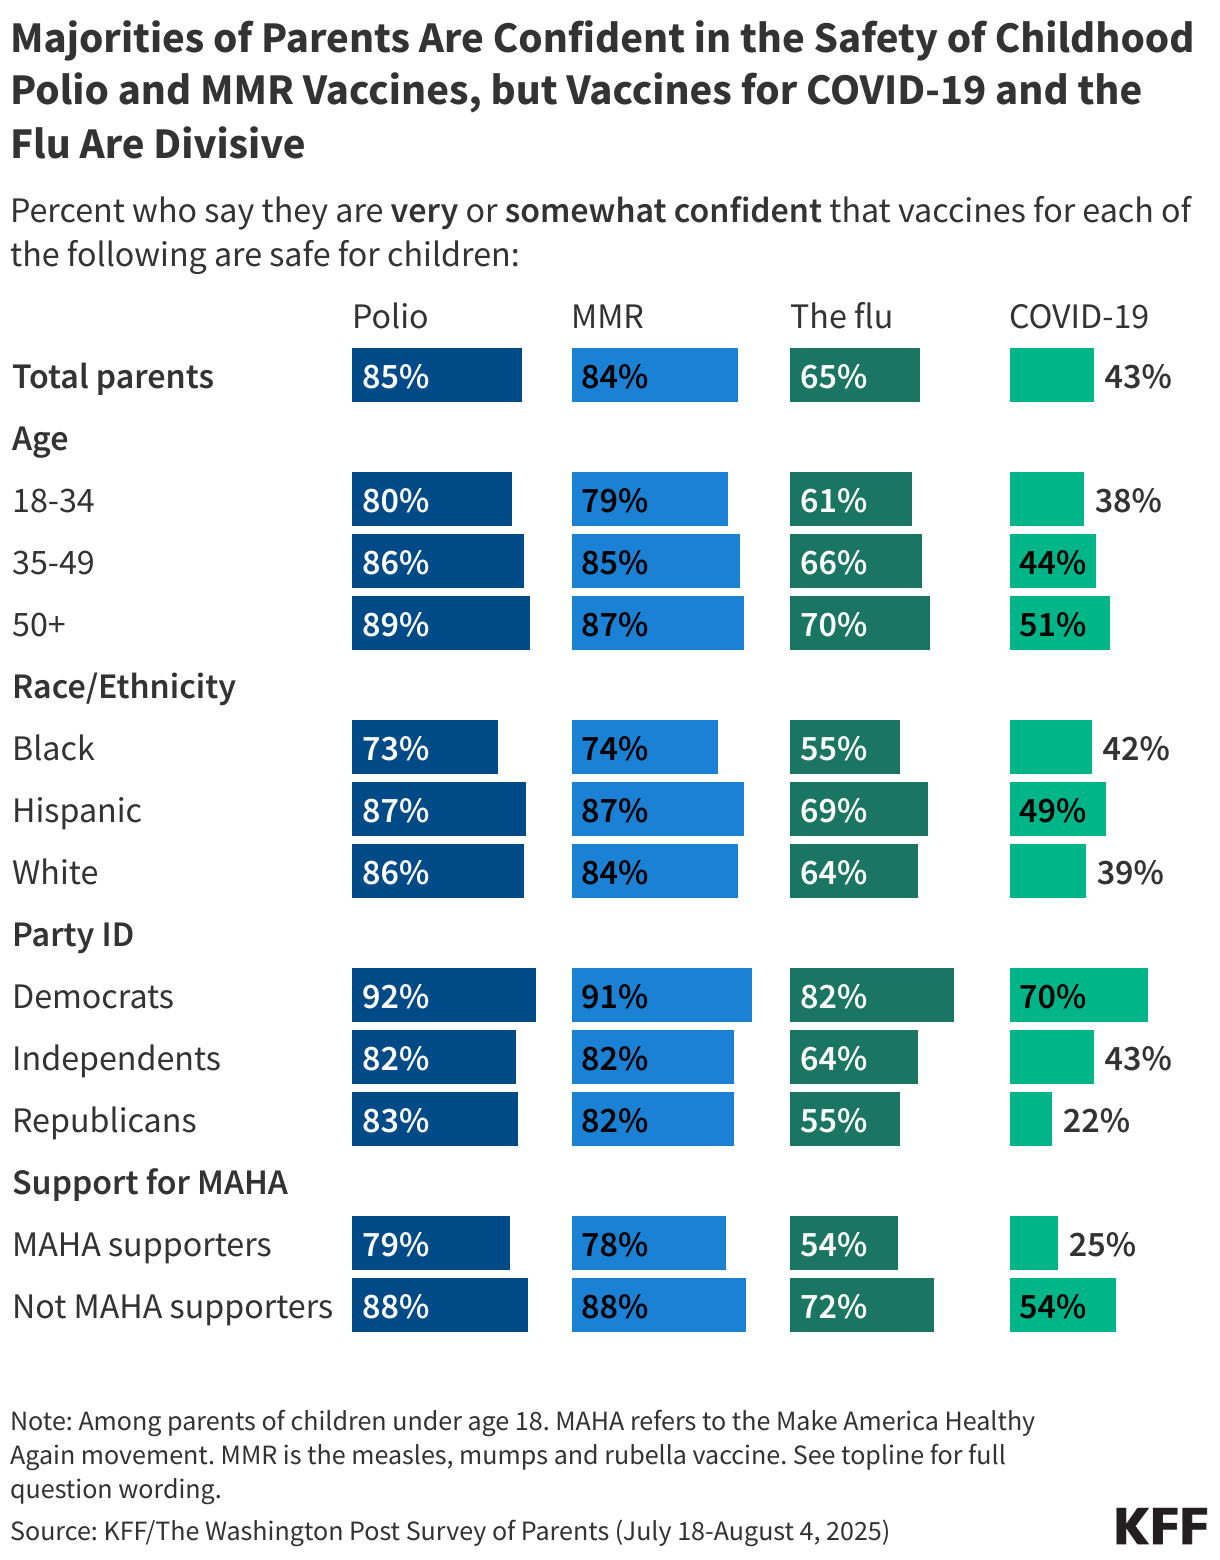
In summer 2025, large majorities of parents expressed confidence in the safety of childhood vaccines for polio and measles, mumps, and rubella (MMR), but parents’ views on the safety of flu and COVID-19 vaccines were more polarized. About two-thirds of parents say the flu vaccines are safe for children, while fewer than half say the same about COVID-19 vaccines, with divisions along partisan lines. Beyond partisanship, parents who support the Make America Healthy Again (MAHA) movement (38% of parents), Black parents and parents under age 35 are less likely than their peers to be confident that many routine vaccines are safe for children. For more information, see the KFF/Washington Post Survey of Parents.

Majorities of Parents Are Confident in the Safety of Childhood Polio and MMR Vaccines, but Vaccines for COVID-19 and the Flu Are Divisive (Split Bars)

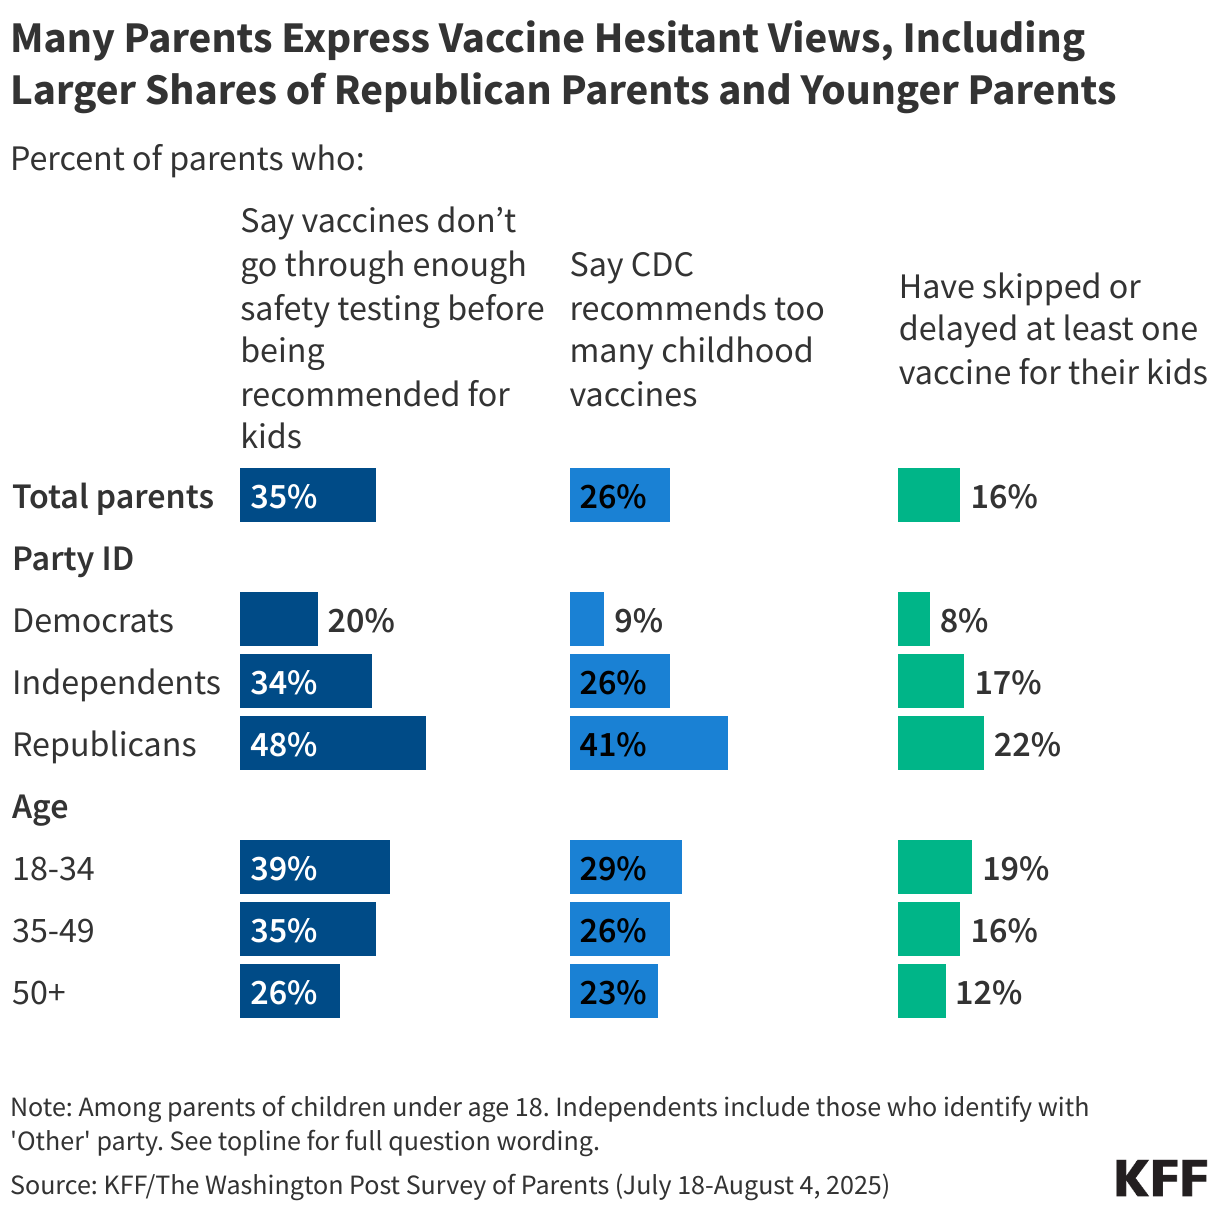
Most parents report keeping their children up to date on childhood vaccines, but about one in six say they have ever skipped or delayed at least one childhood vaccine for any of their children (excluding seasonal vaccines like flu and COVID-19). Despite strong uptake, many parents express skepticism towards vaccine safety testing and the number of vaccines recommended by the CDC (this survey was fielded prior to recent changes to the childhood vaccine schedule announced by HHS in January 2026). Younger parents and those who identify as Republicans are more likely than their counterparts to endorse vaccine-skeptical attitudes and to report skipping vaccines for their own children. For more information, see the KFF/Washington Post Survey of Parents.

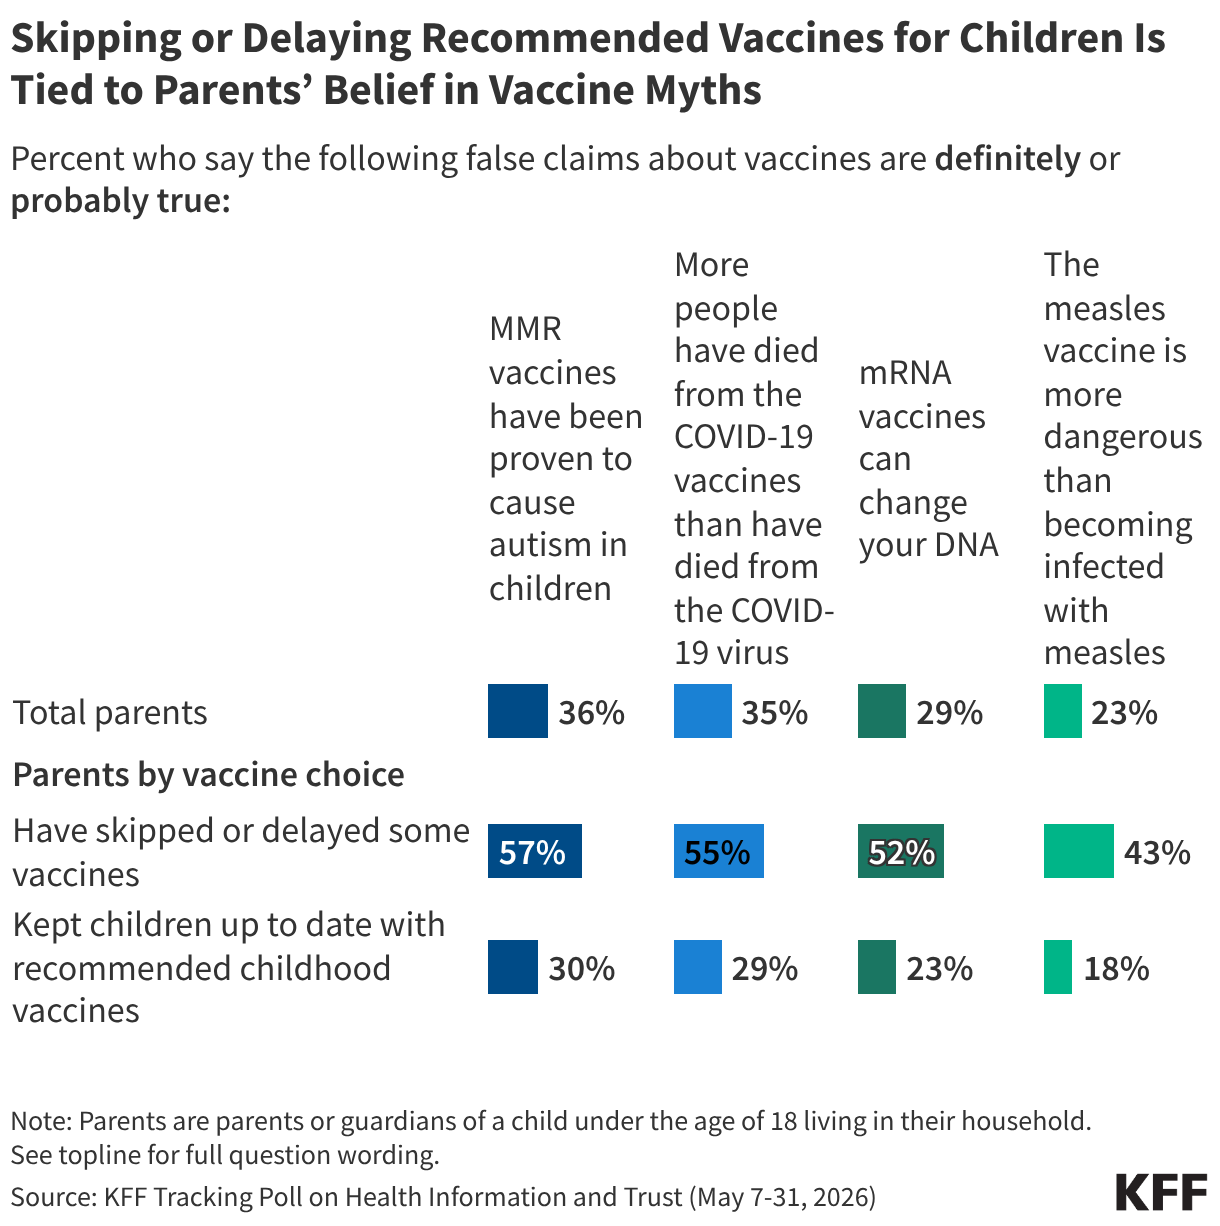
Split bar chart showing percent who say specific false claims about vaccines and diseases are true. Results shown by total parents, parents by vaccine choice, party identification, and support for MAGA.

Parents who skip or delay recommended vaccines for their children are about twice as likely as parents who keep their children up to date on vaccines to believe or lean toward believing false claims about the measles and COVID-19 vaccines, underscoring how false health claims may shape parents’ decisions. For more information, see KFF's June 2026 Tracking Poll on Health Information and Trust.

Split bar chart showing share of U.S. adults who say they believe about each of three false claims related to measles.

mRNA Vaccine Safety

Copy link to mRNA Vaccine Safety

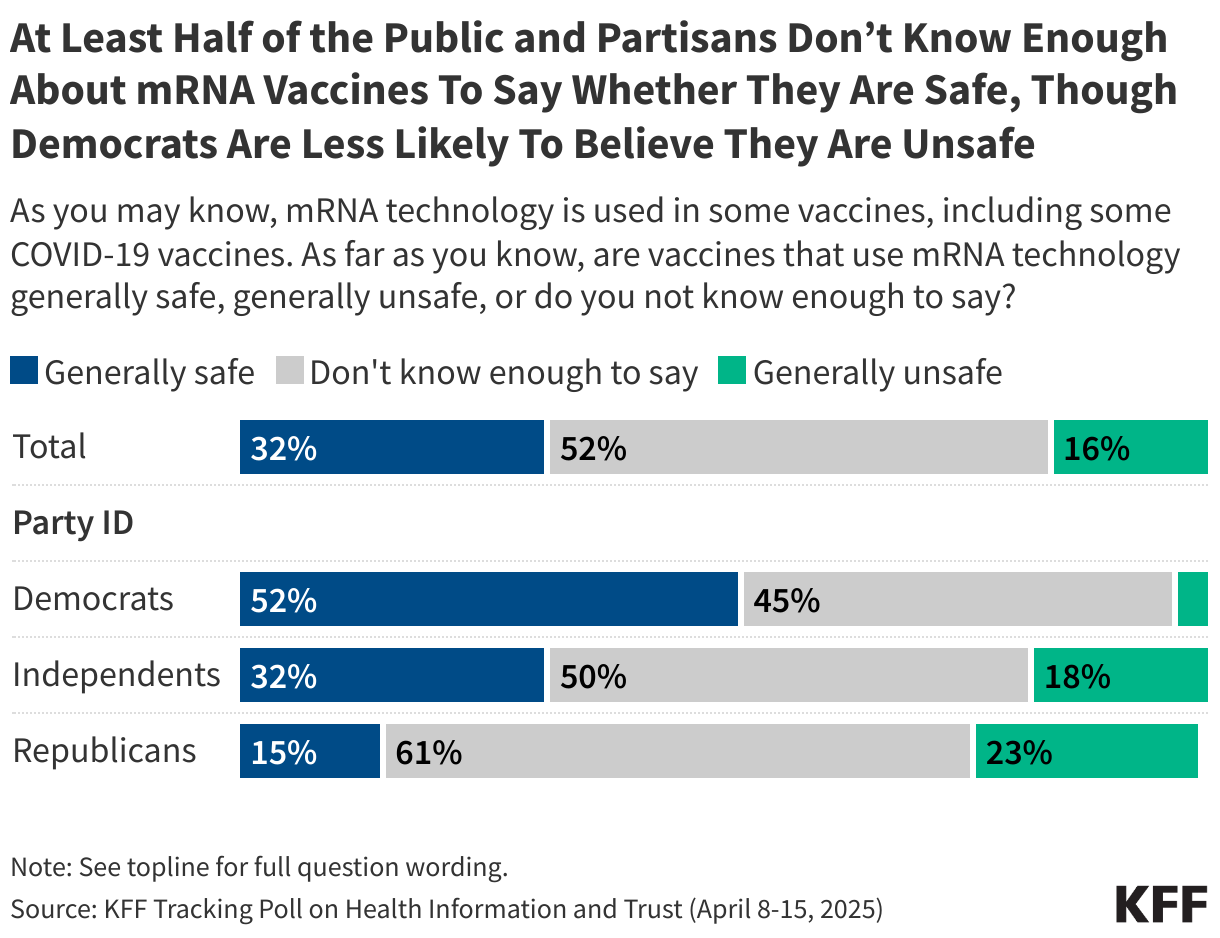
COVID-19 vaccines and some other vaccines currently under development rely on a vaccine technology known as messenger-RNA (mRNA), which has long been the subject of misinformation. While few adults view mRNA technology as unsafe, the technology remains obscure to much of the public, with about half saying they don’t know enough to say. For more information, see KFF’s April 2025 Tracking Poll on Health Information and Trust.

Stacked bar chart showing how safe U.S. adults, by partisanship, think mRNA technology in vaccines is.
Poll Finding

KFF Tracking Poll on Health Information and Trust: Fall 2026 Update on Vaccine Views

Published: Oct 20, 2026

Key Takeaways

  • In the months following two events that put vaccine safety in the spotlight—President Trump’s executive order calling for a change in U.S. childhood vaccine recommendations and the U.S. Senate investigation into Dr. Anthony Fauci—the latest KFF Tracking Poll on Health Information and Trust finds that while confidence in most childhood vaccines remains high, partisans are divided in their views of COVID-19 vaccine safety for both children and pregnant women. At the same time, notable shares of the public and parents express uncertainty or hold misperceptions related to the vaccine discussions at the center of these recent news events.
  • As parents are faced with conflicting advice about how to handle their children’s vaccines, there are differences by partisanship on the best way forward. Overall, about half of parents think children are healthier when vaccines are spaced out and they do not get multiple shots in a single visit while the other half say there is no strong evidence that it’s healthier to do so. Larger shares of Republican parents say it’s better to space vaccines out and seven in ten Democratic parents say there’s no evidence to support this. While spacing out vaccines and refraining from getting multiple shots in one visit are key directives in President Trump’s executive order, there is no evidence to support such claims.
  • Overall confidence in the safety of long-standing vaccines for children is bipartisan, with large majorities of parents and adults across partisanship saying they are confident the polio and MMR vaccines are safe for children. Smaller shares, though still majorities across partisanship, express confidence in the safety of hepatitis B and flu vaccines for children, but views of these two vaccines vary by partisanship with Republicans less confident than Democrats.
  • Views of the safety of COVID-19 vaccines remain very polarized. While half of the public say they are confident the vaccines are safe for children, this is true of 77% of Democrats but just 21% of Republicans. Similarly, four in ten adults overall are confident these vaccines are safe for pregnant people, including 62% of Democrats but just 17% of Republicans. Most adults, including eight in ten women of reproductive age, also express uncertainty about whether getting vaccinated for COVID-19 while pregnant increases the risk of miscarriage—a false claim revived by some Republican senators amid Dr. Fauci’s trial.
  • Many supporters of the Make America Healthy Again (MAHA) movement, a movement often associated with vaccine skepticism, have confidence in the safety of several vaccines for children, including three-quarters who are confident the vaccines for MMR (76%) and polio (76%) are safe and at least half who say the same of hepatitis B and flu vaccines. However, just three in ten are confident in the safety of COVID-19 vaccines for children.

Views of Childhood Vaccine Safety

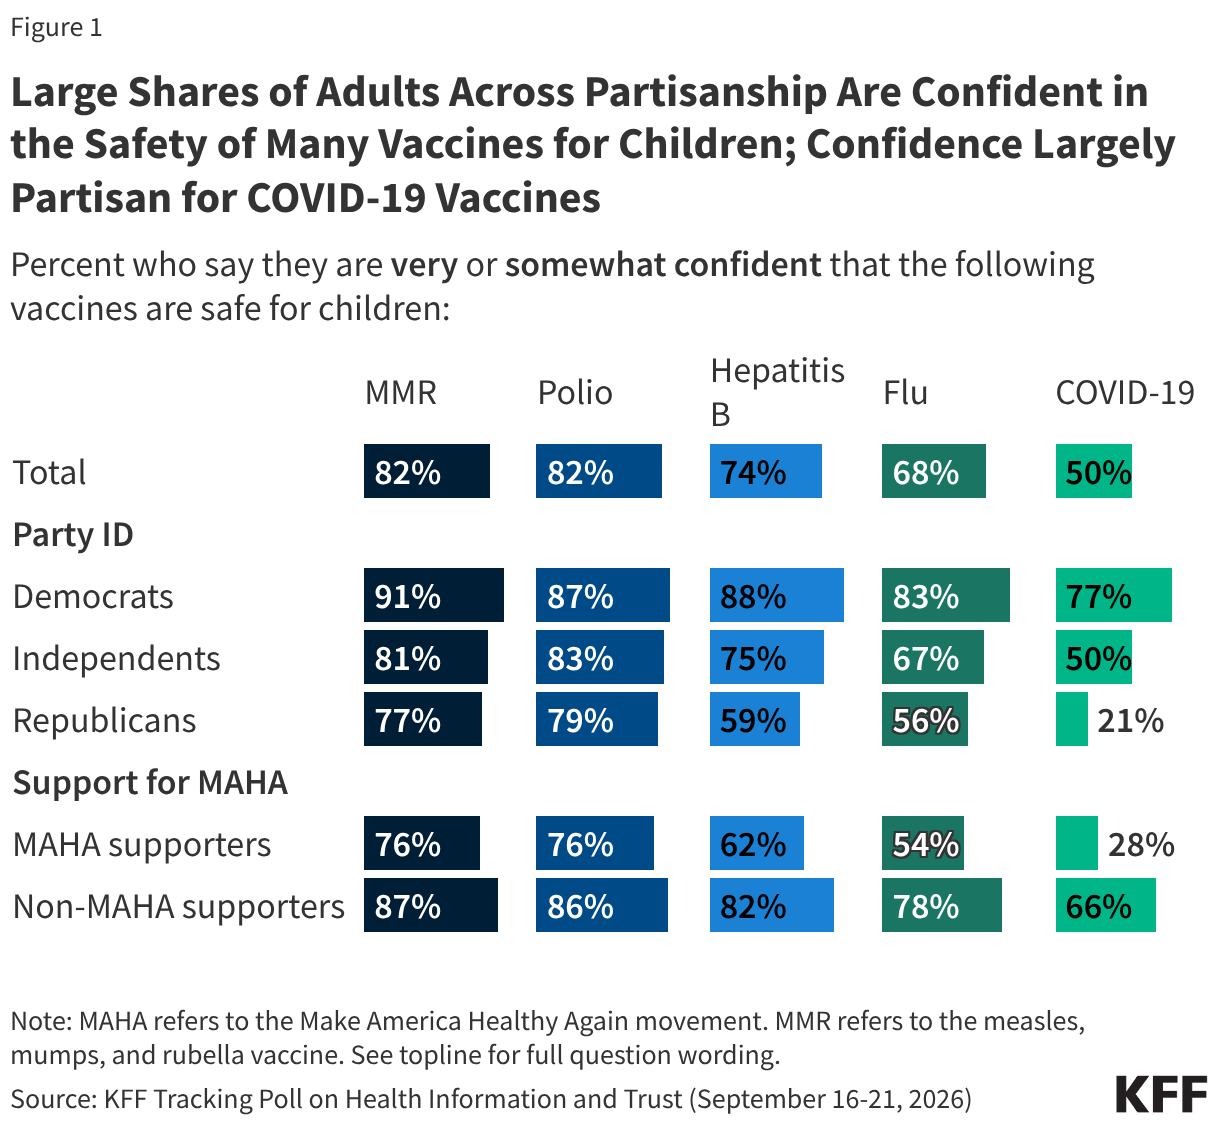
Consistent with prior KFF polling, most adults remain confident in the safety of long-standing childhood vaccines, with at least three-quarters across partisanship saying they are “very” or “somewhat” confident that the polio and the measles, mumps, and rubella (MMR) vaccines are safe for children. Majorities of adults also express confidence in flu and hepatitis B vaccines for children, though there are larger partisan differences on these vaccines, with at least eight in ten Democrats saying they are confident compared to closer to six in ten Republicans.

Confidence in the safety of COVID-19 vaccines for children is deeply divided; half of the public are confident they’re safe for children, though just two in ten (21%) Republicans say this compared to half of independents and three-quarters (77%) of Democrats. Influenza (flu), hepatitis B, and COVID-19 are included in the list of immunizations the Trump administration is seeking to shift from routine use to shared clinical decision-making (and for children who meet certain risk criteria in the case of hepatitis B) in the most recent executive order changing the childhood vaccine schedule and in earlier attempts this year. The changes outlined in the executive order remain blocked in federal courts for now.

Notably, many supporters of the Make America Healthy Again movement (who make up 42% of the public)—a movement that has often been associated with vaccine skepticism—have confidence in the safety of several vaccines for children; three-quarters of this group express confidence in vaccines for MMR (76%) and polio (76%) and over half are confident in vaccines for hepatitis B (62%) and the flu (54%). A much smaller share (28%) of MAHA supporters are confident in COVID-19 vaccine safety for children.

Overall, confidence in the safety of all vaccines asked about in this survey for children remains largely unchanged from January and May of this year among parents, across partisans, among MAHA supporters, and among adults overall.

Split bar chart showing percent who say they are very or somewhat confident that specific vaccines are safe for children. Results shown by total adults, party identification, and support for the Make America Healthy Again movement.

Similar to the overall public, there are notable partisan divides among parents of children under 18 when it comes to vaccine confidence; while large majorities of parents across partisanship are confident in the safety of childhood vaccines for MMR and polio, parents who are Democrats or Democratic-leaning independents are at least 20 percentage-points more likely to express confidence in hepatitis B and flu vaccines for children compared to their Republican counterparts. And, like partisans overall, the divides are largest for COVID-19 vaccines, with Democratic parents three times more likely to say the vaccines are safe compared to Republican parents (64% vs. 19%).
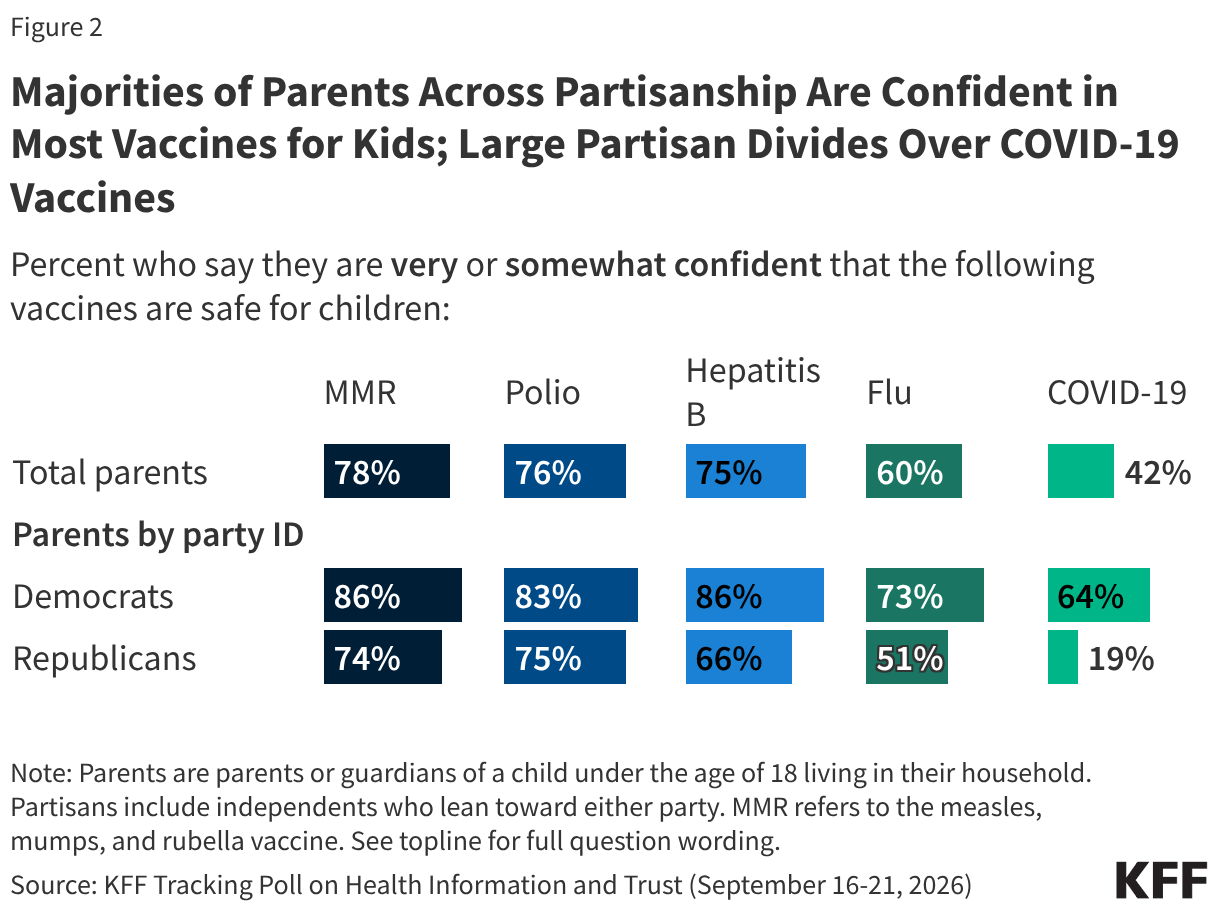
Split bar chart showing percent who say they are very or somewhat confident that specific vaccines are safe for children. Results shown by total parents and parents by party identification.

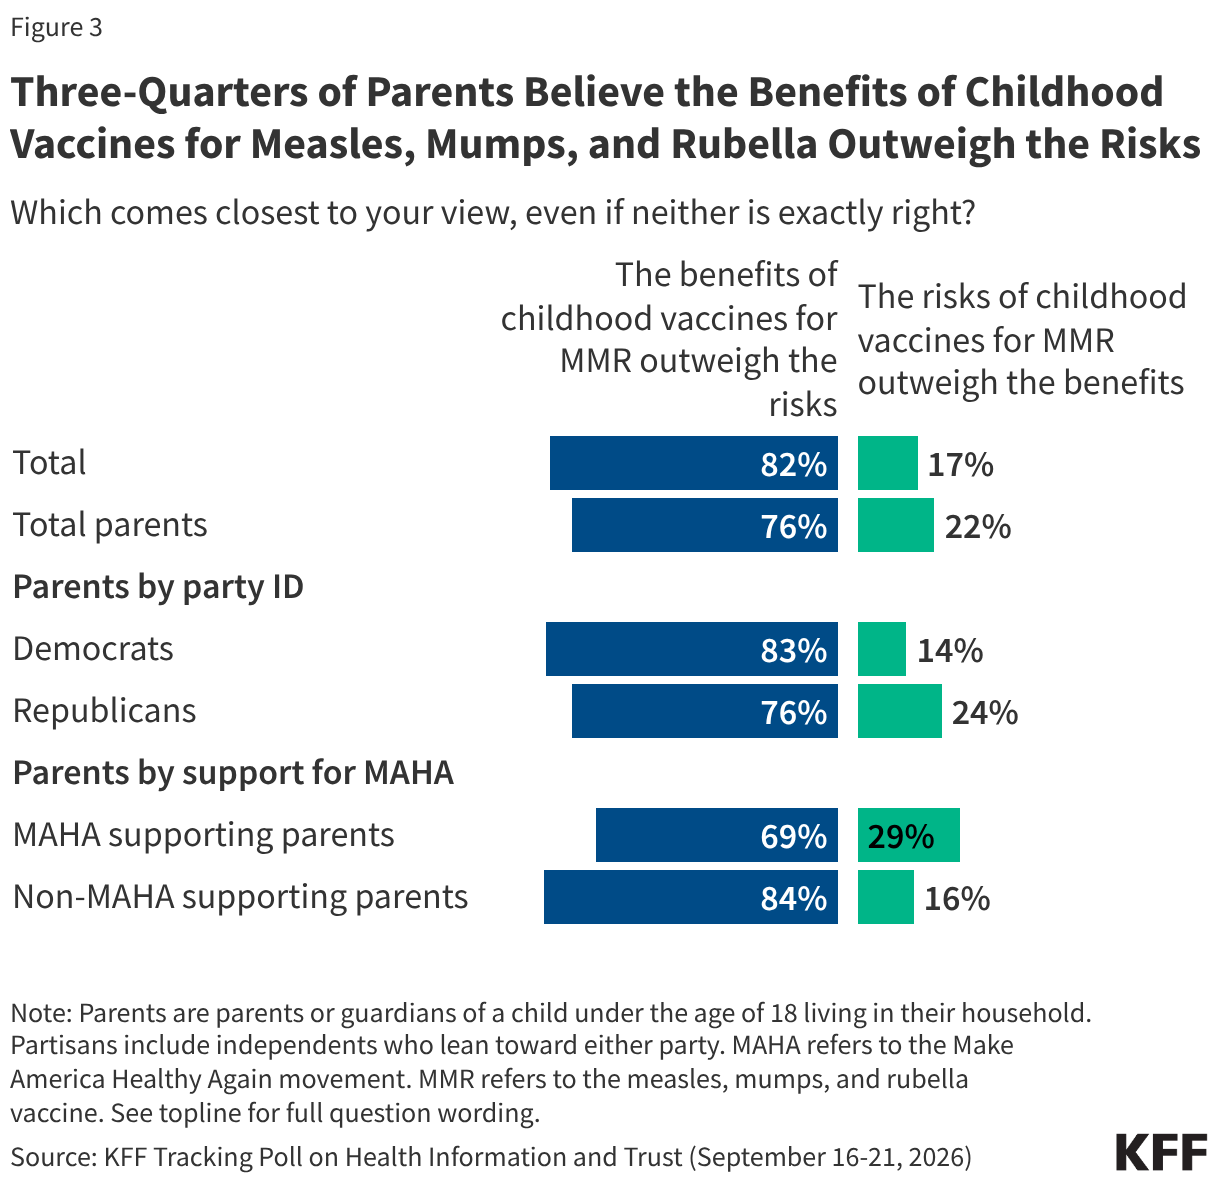
In addition to their general confidence in the safety of long-standing childhood vaccines, eight in ten (82%) adults overall and three quarters (76%) of parents think the benefits of childhood vaccines for MMR outweigh the risks while about one in five (17% of all adults; 22% of parents) say the risks outweigh the benefits. These shares have largely stayed consistent since the beginning of the second Trump administration, before many changes to the vaccine policy recommendations. Large shares of parents across partisanship say the benefits of MMR vaccines outweigh the risks, though Republican or Republican-leaning parents are somewhat more likely than Democrat or Democratic-leaning parents to say the risks outweigh the benefits (24% vs. 14%).

Even among parents who support the Make America Healthy Again movement, seven in ten (69%) say the benefits of MMR vaccines outweigh the risks, though the share of MAHA parents who say the risks outweigh the benefits is larger than among parents who do not support MAHA (29% vs. 16%).

Split bar chart showing percent who say the benefits of childhood vaccines for MMR outweigh the risks or vice versa. Results shown by total adults, total parents, parents by party identification, and parents by their support for the Make America Healthy Again movement.

Awareness and Perceptions of the Recent Vaccine Executive Order

The executive order signed by President Trump in August calls for the reduction in the number of diseases targeted by routine childhood vaccination from 17 to 11 and calls for the measles, mumps, and rubella (MMR) vaccines to be administered as separate vaccines, among other directives.

Most (59%) of the public, and a similar share of parents, have heard either “not much” (30%) or “nothing at all” (28%) about the most recent attempts by the administration to change the childhood vaccine schedule, while a smaller share (41%) of adults say they have heard “some” (30%) or “a lot” (12%) about it. By comparison, about half (51%) reported hearing at least “some” about similar changes to the vaccine schedule announced in January.
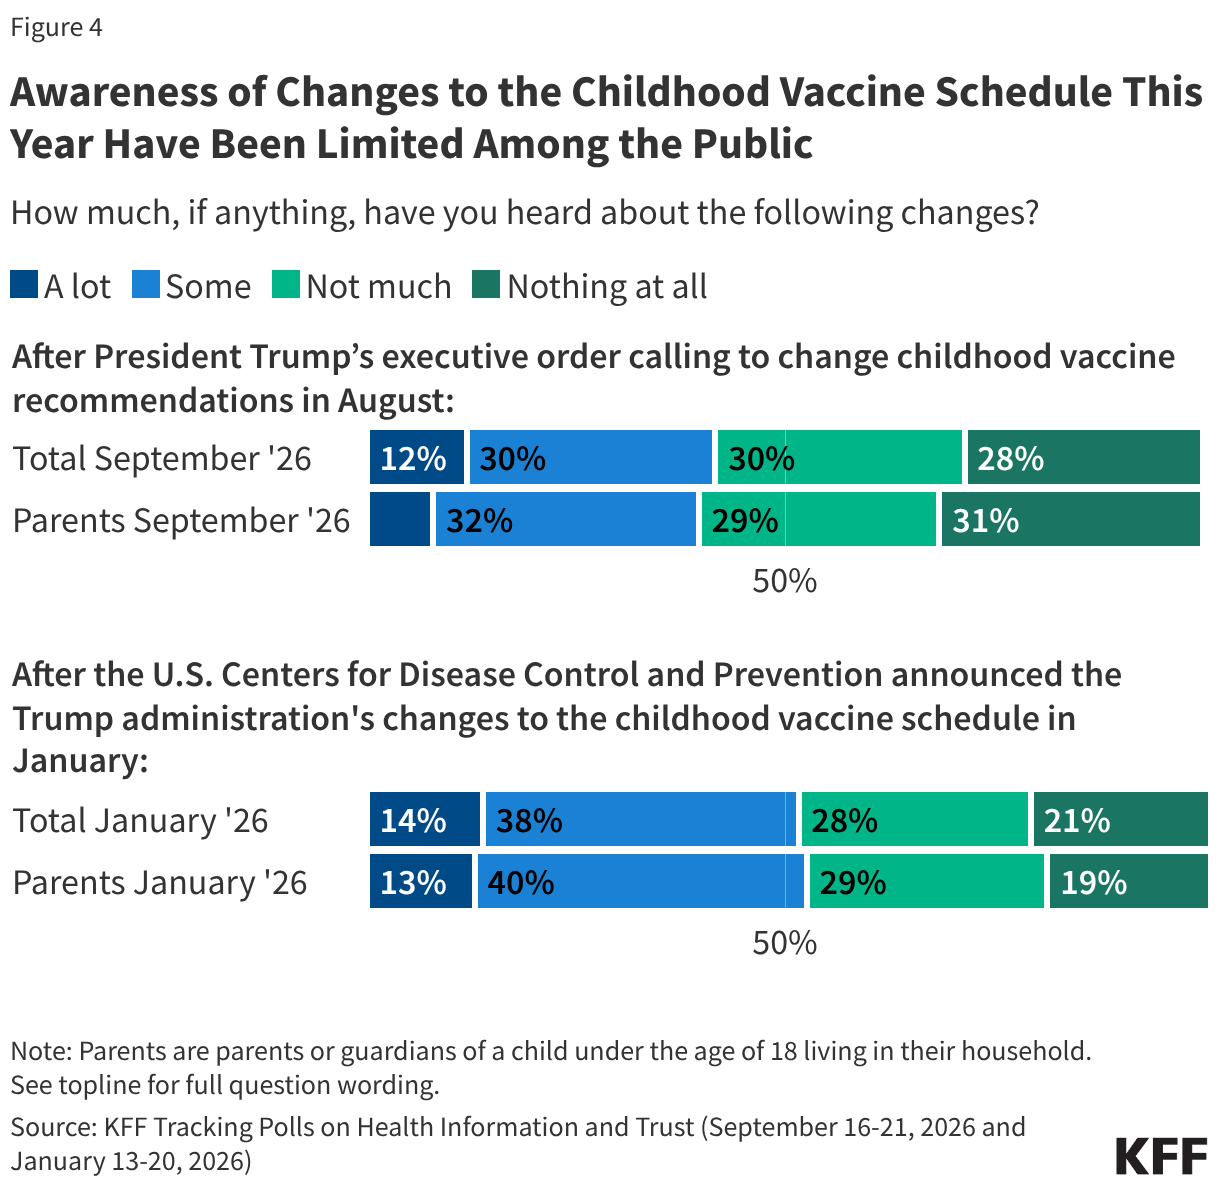
Stacked bar chart showing percent who have heard of the recent changes to the childhood vaccine schedule. Results shown among total adults and parents in September 2026 and in January 2026.

While many adults are unsure about the federal government’s recent executive order on childhood vaccines, views of how these changes might affect children’s health are more negative than positive. Four in ten overall think these changes will have a negative impact on children’s health in the U.S., one in eight (12%) say they will have a positive impact, one in ten (9%) say they will have no impact, and four in ten (38%) are unsure. These perceptions vary greatly by partisanship, with Democrats and independents much more likely to view the impact as negative rather than positive. Republicans are more likely to say the changes will have a positive impact (27%) than a negative one (9%), but half of Republicans say they are unsure.

Notably, half of parents say the changes to the childhood vaccine schedule will have either no impact (14%) on children’s health in the U.S. or are unsure of the impact they will have (36%). Among supporters of the Make America Healthy Again (MAHA) movement, half (48%) are unsure of the impact the changes will have, while smaller, similar shares say it will have either a positive (23%) or negative (18%) impact.

Among the 41% of the public who have heard “a lot” or “some” about the recent executive order, six in ten (60%) say the changes will have a negative impact on children’s health, about three times the share who expect a positive impact (18%).
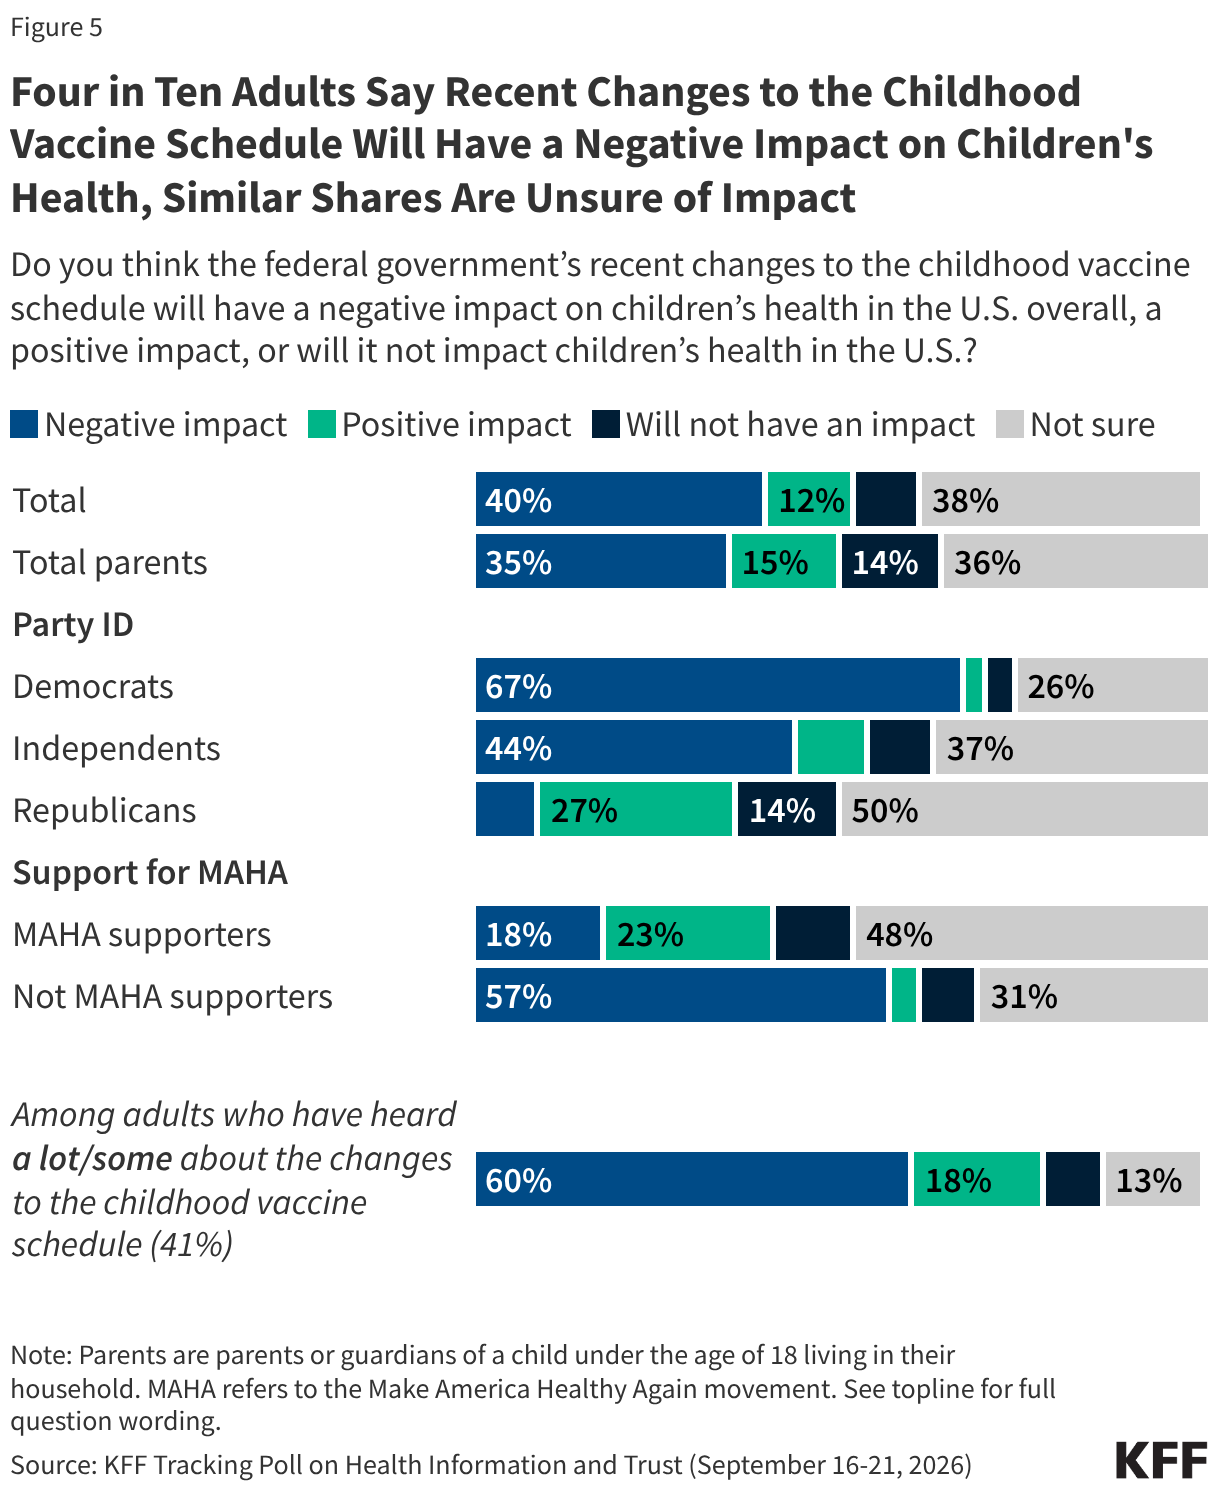
Stacked bar chart showing percent who say the federal government's updates to the childhood vaccine schedule will have a negative impact, a positive impact, or no impact on children's health in the U.S. Results shown by total adults, total parents, party identification, and support for the Make America Healthy Again movement.

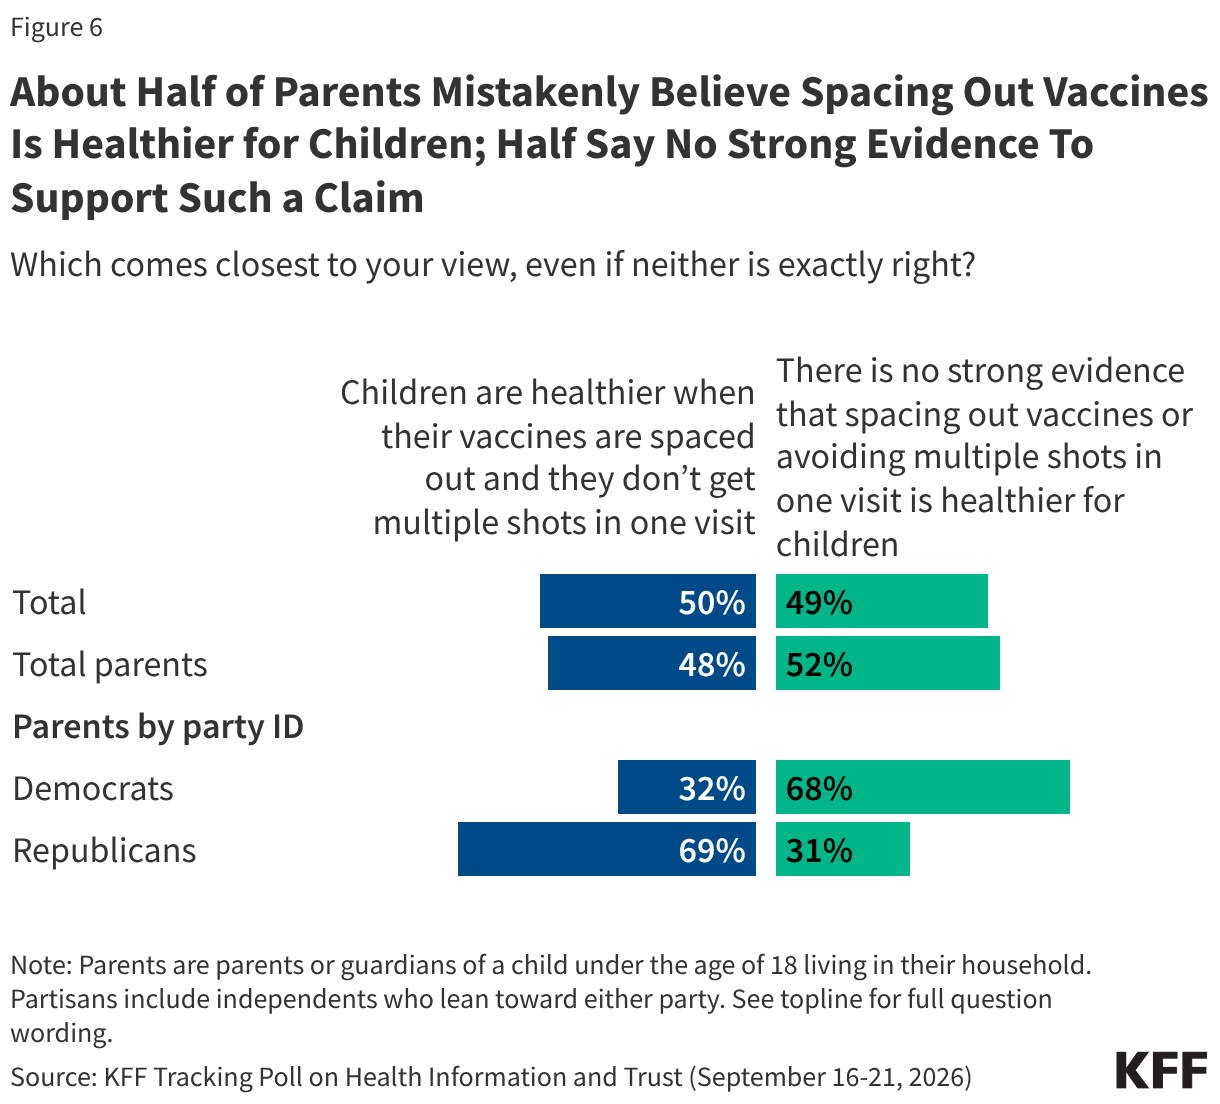
Alongside reductions to the number of diseases targeted by routine childhood vaccination, the recent executive order calls for separate doses for the currently combined MMR vaccine. This directive also comes at a time when the President has made statements that spacing out and separating doses of childhood vaccines would reduce autism rates. The KFF Tracking Poll on Health Information and Trust finds parents are divided in their perceptions of whether it is healthier for childhood vaccines to be spaced out. Half of parents (48%) incorrectly think children are healthier when their vaccines are spaced out and they don’t get multiple shots in one visit, while another half (52%) says there is no strong evidence to support such a claim. There is no evidence that spacing out vaccines is safer for children, however this perception among parents is not new; previous KFF polling has found concerns about receiving multiple vaccines at once is one of the top reasons parents report skipping or delaying childhood vaccines.

Awareness of whether childhood vaccines are safer when spaced out varies by partisanship, with seven in ten (68%) Democratic or Democratic-leaning parents saying there is no strong evidence that it is healthier for children to space out vaccines or avoid multiple shots in one visit, while a similar share of Republicans or Republican-leaning parents (69%) say children are healthier this way.

Split bar chart showing percent who say children are healthier when their vaccines are spaced out versus percent who say there is no strong evidence to suggest spacing out vaccines is healthier. Results shown by total adults, total parents, and parents by party identification.

Misperceptions About COVID-19 Vaccine Safety in Pregnancy

Misinformation about the COVID-19 vaccine and its effects on pregnancy, breastfeeding, and fertility have been widespread over the years, including recent claims tying the vaccine to first trimester miscarriages. About four in ten (39%) adults say they are either “very” or “somewhat” confident that the COVID-19 vaccines are safe for pregnant people, a decrease from 53% in May 2022. Among women of reproductive age, 37% now have confidence in the vaccines’ safety during pregnancy, down from 48%. As with most attitudes toward COVID-19 vaccines, there are large partisan gaps, with more than six in ten (62%) Democrats expressing confidence and more than eight in ten (83%) Republicans saying they are not confident. Notably, confidence in COVID-19 vaccine safety for pregnant people has decreased across partisans since 2022, including a 17-percentage point decrease in confidence among Democrats and a 15-percentage point decrease among Republicans.
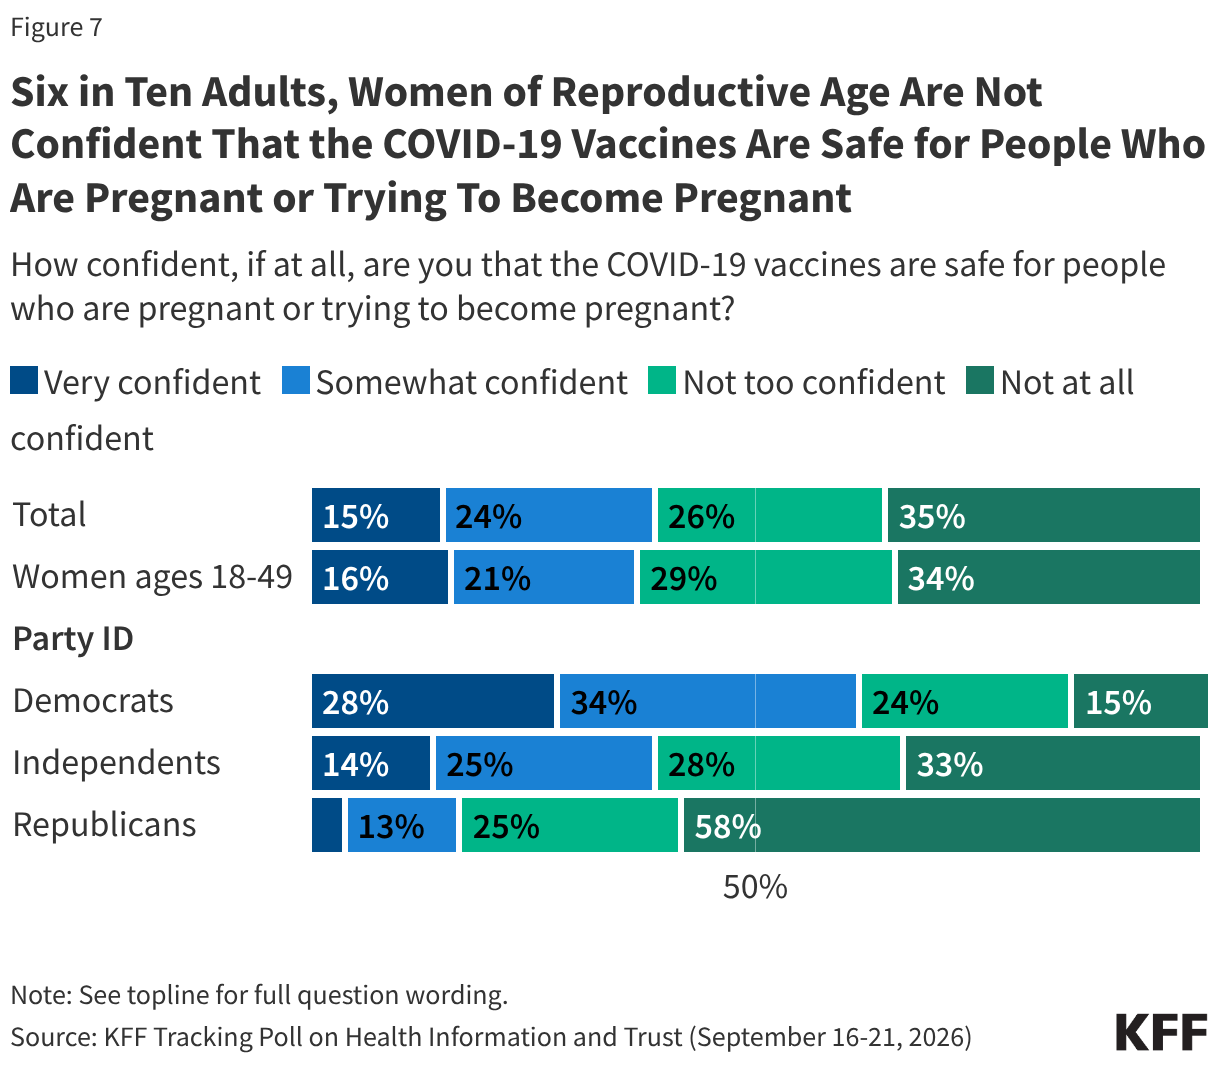
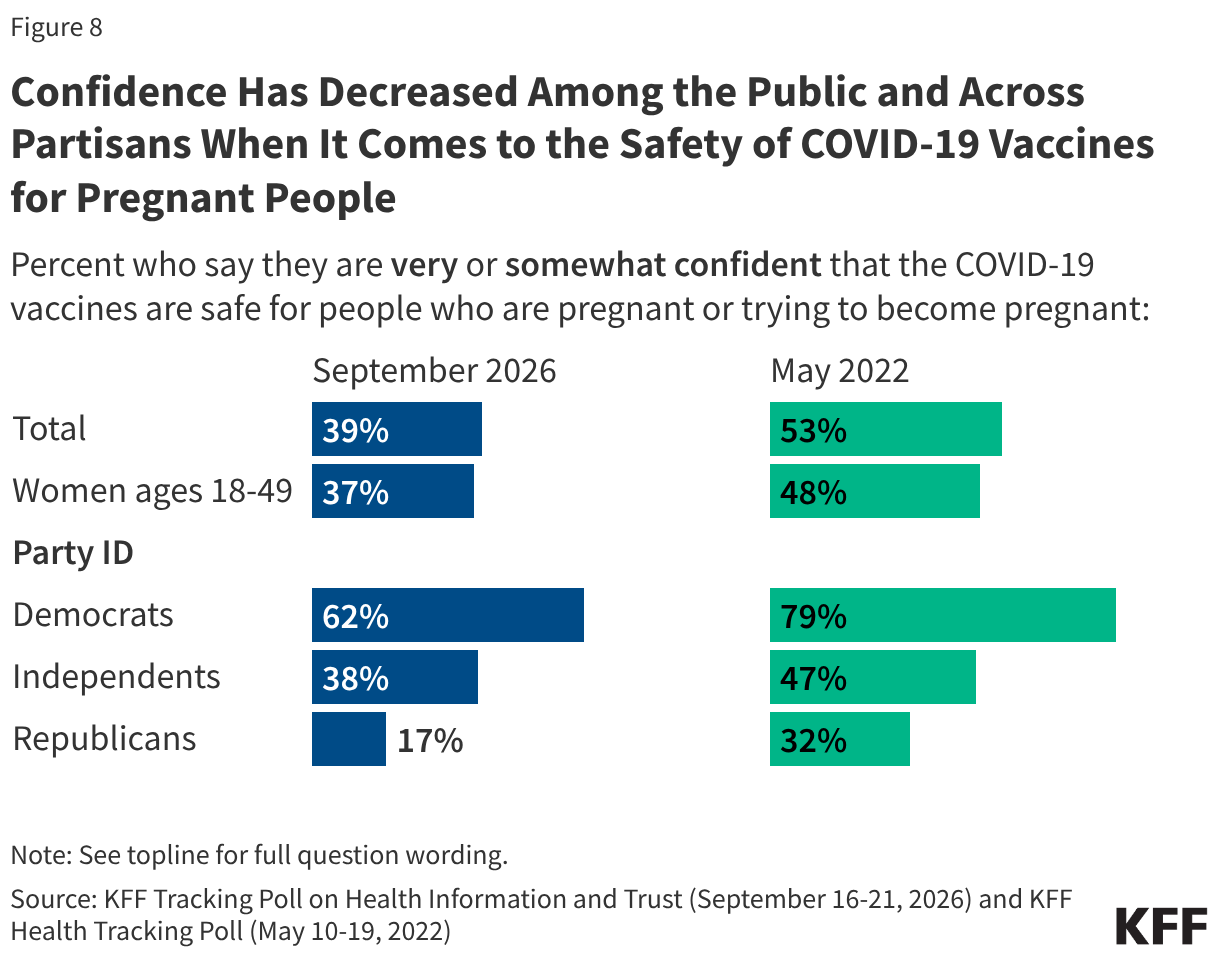
Stacked bar chart showing confidence levels in the safety of the COVID-19 vaccines for people who are pregnant or trying to become pregnant. Results shown by total adults, women of reproductive age, and party identification.
Split bar chart showing percent who say they are very or somewhat confident that the COVID-19 vaccines are safe for people who are pregnant or trying to become pregnant in September 2026 versus May 2022. Results shown by total adults, women of reproductive age, and party identification.

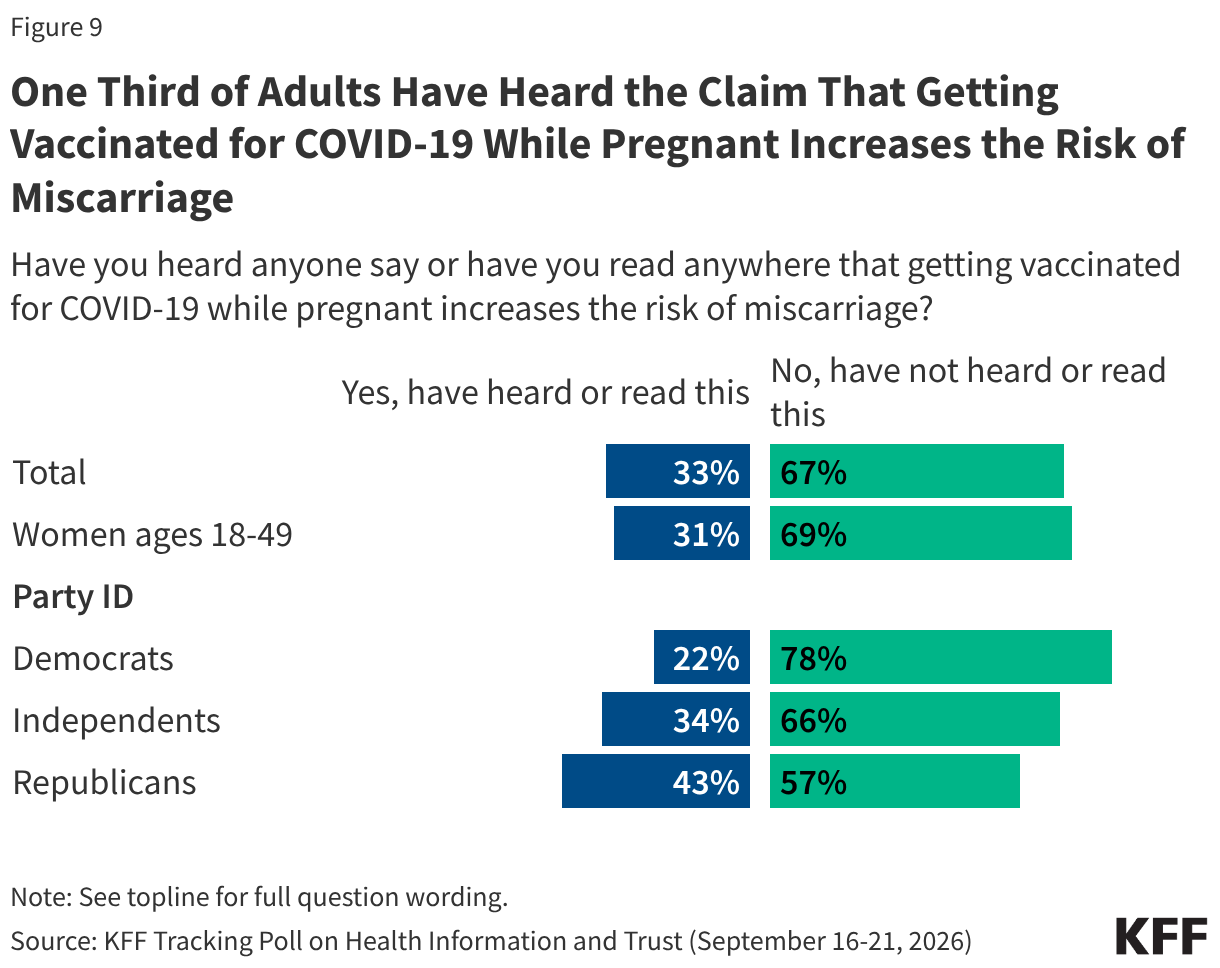
The decrease in confidence in COVID-19 vaccine safety for pregnant people comes amid revived false claims linking COVID-19 vaccination to miscarriage, a claim which leaves many adults uncertain. About a third of the public have heard the claim that getting vaccinated for COVID-19 while pregnant increases the risk of miscarriage, including about four in ten Republicans (43%), a third of independents (34%), and one in five Democrats (22%). Three in ten (31%) women of reproductive age (ages 18 to 49) also say they have heard this.

Split bar chart showing percent who say they have heard anyone say or have read anywhere that getting vaccinated for COVID-19 while pregnant increases the risk of miscarriage. Results shown by total adults, women of reproductive age, and party identification.

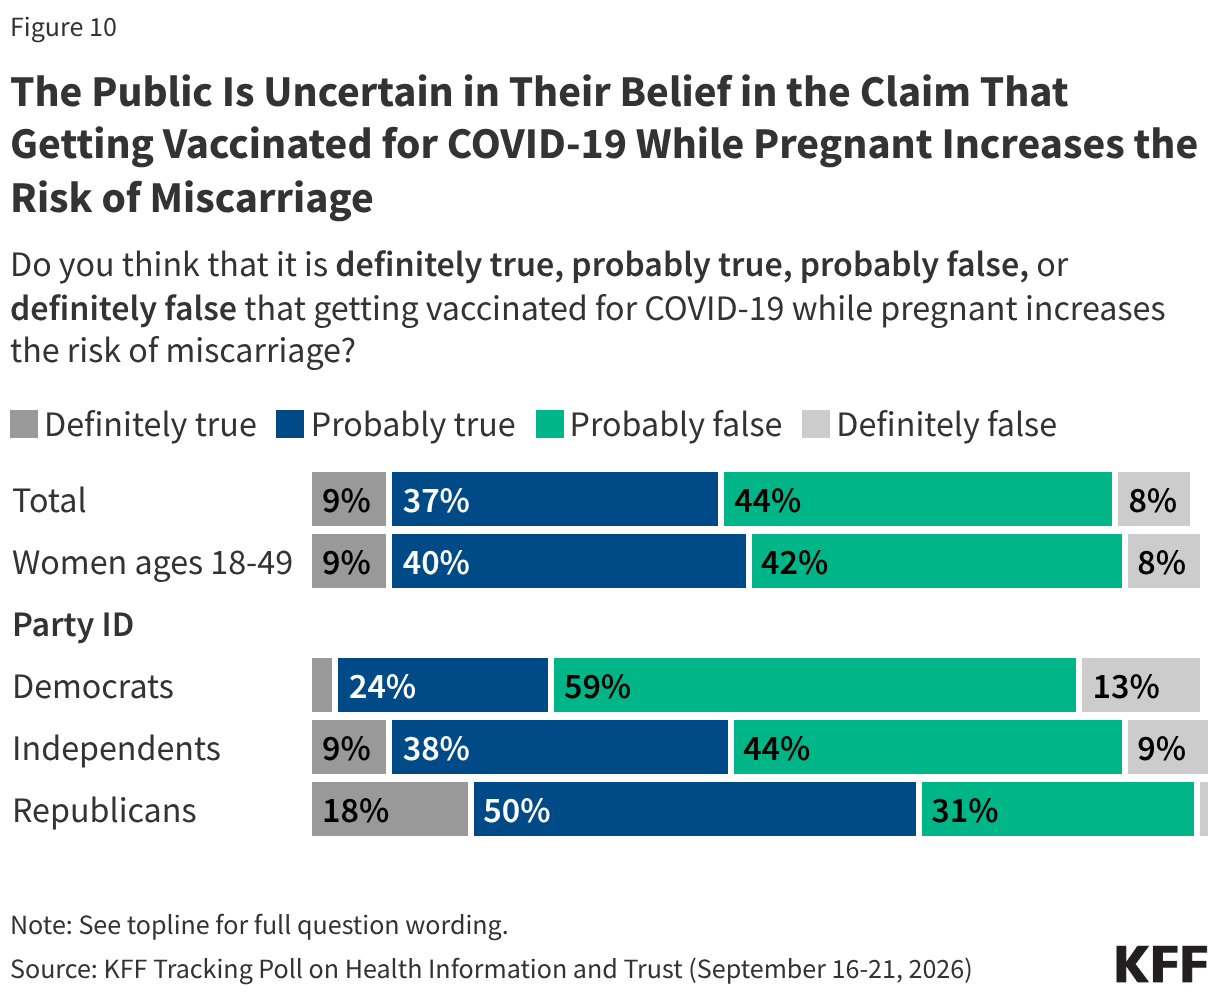
While research has consistently found COVID-19 vaccines to be safe for pregnant people, many adults are still uncertain about potential links between the vaccines and miscarriages. A small share of the public, just 8%, say it is “definitely false” that getting vaccinated for COVID-19 while pregnant increases the risk of miscarriage, and a similar share say the claim is “definitely true” (9%).

In line with KFF’s Health Information and Trust research on a variety of health topics, many adults fall in the “malleable middle” when it comes to this claim, saying it is either “probably true” (37%) or “probably false” (44%). The large share of adults who express uncertainty about this claim is consistent across partisanship, though a somewhat larger share of Republicans say it is “definitely true” (18%) while more Democrats say it is “definitely false” (13%). A large majority of women of reproductive age also express uncertainty about this claim, with equal shares saying it is either “probably true” (40%) or “probably false” (42%).

Stacked bar chart showing belief in the claim that getting vaccinated for COVID-19 while pregnant increases the risk of miscarriage. Results shown by total adults, women of reproductive age, and party identification.

This KFF Health Tracking Poll/KFF Tracking Poll on Health Information and Trust was designed and analyzed by public opinion researchers at KFF. The survey was conducted September 16 – September 21, 2026, online and by telephone among a nationally representative sample of 1,328 U.S. adults in English (n=1,237) and in Spanish (n=91). The sample includes 1,015 adults (n=72 in Spanish) reached through the SSRS Opinion Panel either online (n=990) or over the phone (n=25). The SSRS Opinion Panel is a nationally representative probability-based panel where panel members are recruited randomly in one of two ways: (a) Through invitations mailed to respondents randomly sampled from an Address-Based Sample (ABS) provided by Marketing Systems Groups (MSG) through the U.S. Postal Service’s Computerized Delivery Sequence (CDS); (b) from a dual-frame random digit dial (RDD) sample provided by MSG. For the online panel component, invitations were sent to panel members by email followed by up to three reminder emails.
Another 313 (n=19 in Spanish) adults were reached through random digit dial telephone sample of prepaid cell phone numbers obtained through MSG. Phone numbers used for the prepaid cell phone component were randomly generated from a cell phone sampling frame with disproportionate stratification aimed at reaching Hispanic and non-Hispanic Black respondents. Stratification was based on incidence of the race/ethnicity groups within each frame. Among this prepaid cell phone component, 142 were interviewed by phone and 171 were invited to the web survey via short message service (SMS).

Respondents in the prepaid cell phone sample who were interviewed by phone received a $15 incentive via a check received by mail or an electronic gift card incentive. Respondents in the prepaid cell phone sample reached via SMS received a $10 electronic gift card incentive. SSRS Opinion Panel respondents received a $5 electronic gift card incentive (some harder-to-reach groups received a $10 electronic gift card). In order to ensure data quality, cases were removed if they failed two or more quality checks: (1) attention check questions in the online version of the questionnaire, (2) had over 30% item non-response, or (3) had a length less than one quarter of the mean length by mode. Based on this criterion, 8 cases were removed.

The combined cell phone and panel samples were weighted to match the sample’s demographics to the national U.S. adult population using data from the Census Bureau’s 2025 Current Population Survey (CPS), September 2023 Volunteering and Civic Life Supplement data from the CPS, and the 2026 KFF Benchmarking Survey with ABS and prepaid cell phone samples. The demographic variables included in weighting for the general population sample are gender, age, education, race/ethnicity, region, civic engagement, frequency of internet use and political party identification. The weights account for differences in the probability of selection for each sample type (prepaid cell phone and panel). This includes adjustment for the sample design and geographic stratification of the cell phone sample, within household probability of selection, and the design of the panel-recruitment procedure.

The margin of sampling error including the design effect for the full sample is plus or minus 3 percentage points. Numbers of respondents and margins of sampling error for key subgroups are shown in the table below. For results based on other subgroups, the margin of sampling error may be higher. Sample sizes and margins of sampling error for other subgroups are available on request. Sampling error is only one of many potential sources of error and there may be other unmeasured error in this or any other public opinion poll. KFF public opinion and survey research is a charter member of the Transparency Initiative of the American Association for Public Opinion Research.


GroupN (unweighted)M.O.S.E.
Total1,328± 3 percentage points
Total registered voters1,013± 4 percentage points
   
Party ID  
Democrats446± 6 percentage points
Independents439± 6 percentage points
Republicans347± 7 percentage points
   
Registered Voter Party ID  
Democrats379± 6 percentage points
Independents304± 7 percentage points
Republicans294± 7 percentage points
   
MAHA Support  
Adults who support the MAHA movement565± 5 percentage points
Adults who do not support the MAHA movement742± 5 percentage points
   
Parents of Children Under 18437± 6 percentage points
Democrats/Democratic-leaning parents197± 9 percentage points
Republican/Republican-leaning parents149± 10 percentage points
Parents who support the MAHA movement197± 9 percentage points
Parents who do not support the MAHA movement234± 8 percentage points
   
Women Ages 18-49393± 6 percentage points

The Business of Health with Chip Kahn

Building the AI Hospital

October 20, 2026

Video

Audio

About this Episode


Episode 20, AI Series: Walk into the emergency room at Israel’s largest hospital and the first clinician to take your history may be an AI avatar — with a physician signing off on every recommendation. Israel’s Sheba Medical Center is building what could become the first fully AI-based hospital by 2030. Dr. Eyal Zimlichman, Sheba’s Chief Transformation Officer, Chief Innovation Officer and Chief AI officer, talks with Chip about what that means for patients. During their conversation, Dr. Zimlichman argues that in the future, doctors will “be much more humane than the doctors of the present…because if we’re not able to achieve that, then there’s really no difference between the AI and the physician…we will be able to compete with the AI in terms of humanity.”

The Host


Headshot photo of Chip Kahn wearing a navy blue suit with a red tie, red pendant on lapel, and glasses.

Sr. Visiting Fellow

Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.

Guest


Chief Transformation Officer, Chief Innovation Officer, and Chief AI Officer, Sheba Medical Center; Founder, ARC Innovation

Eyal Zimlichman, MD, is a physician, healthcare executive, and researcher specializing in healthcare quality, value, and patient safety. In the separate roles of Chief Transformation Officer, Chief Innovation Officer, and Chief AI Officer at Sheba Medical Center at Sheba Medical Center—Israel’s largest hospital—he drives efforts to make care more patient-centered, efficient, and equitable, and founded ARC (Accelerate, Redesign, Collaborate), Sheba’s global platform for advancing digital health and AI through collaboration with healthcare institutions, industry, and startups. His leadership has earned international recognition, including being named a Chief Transformation Officer to Know by Becker’s Hospital Review in 2023 and 2024. He previously served as Sheba’s Chief Medical Officer and, before that, its Chief Quality Officer. Dr. Zimlichman holds a Master of Science in Healthcare Management from the Harvard T.H. Chan School of Public Health and earned his MD from the Technion – Israel Institute of Technology.


SERIES

This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.

The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.

Medicaid State Fact Sheets

Medicaid and CHIP provide health and long-term care coverage to millions of low-income children and adults in the United States. The programs are jointly financed by the federal government and states and are administered by states within broad federal rules. As a result, programs vary widely across states in how many and which residents they cover and how much they spend. These differences reflect state policy choices, such as whether to adopt the ACA Medicaid expansion or set income limits above federal minimums for certain groups, as well as differences in demographic characteristics of state populations. These fact sheets provide key data on Medicaid programs in every state.

Click a state’s tooltip in the map or the state name in the table below to view the fact sheets.


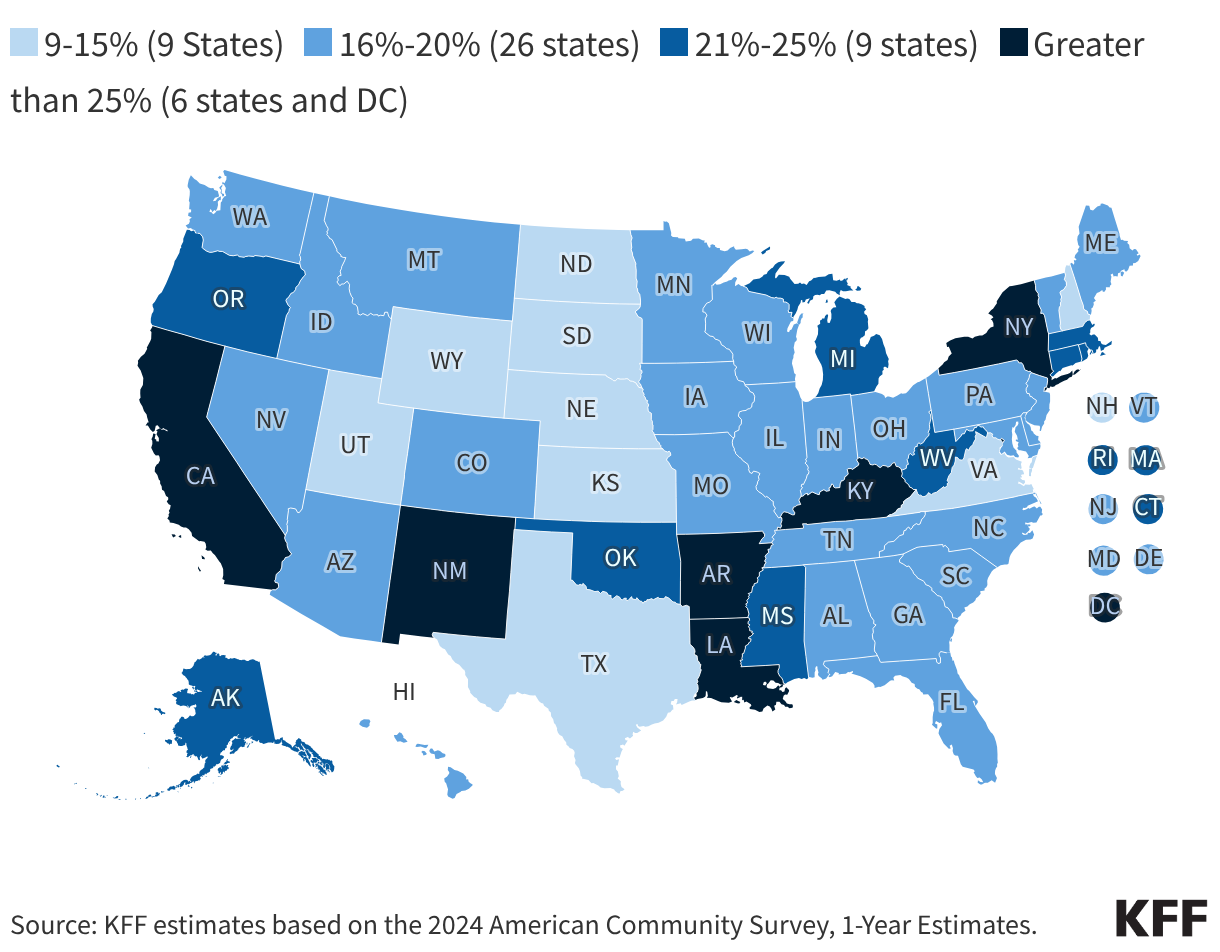
Percent of People Covered By Medicaid, 2024

Choropleth map

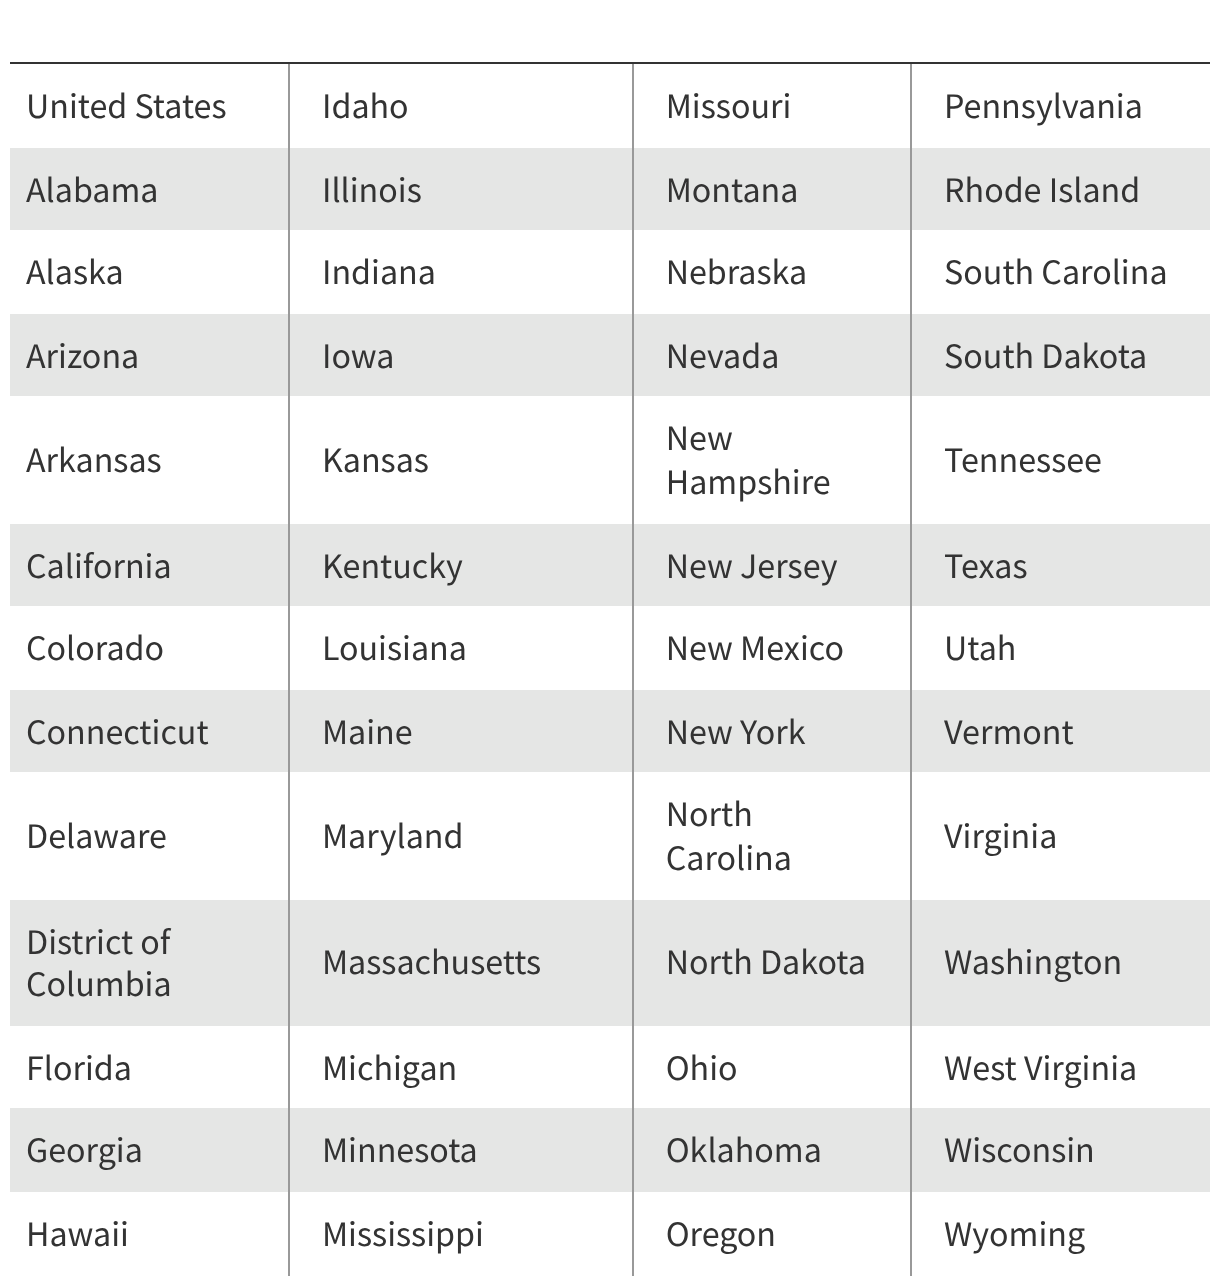
Click on the state name in the table below to download a fact sheet that provides a snapshot of key data for Medicaid in that state.

Table

Sources

The fact sheets include both state and national level data. For specific sources used in the fact sheets, see below.

Total Medicaid Enrollment

State Health Facts, Total Monthly Medicaid & CHIP Enrollment and Pre-ACA Enrollment, June 2026.

Medicaid Covers

Congressional District Maps

KFF, Congressional District Interactive Map: Medicaid Enrollment by Eligibility Group, October 2026.

Medicaid Enrollees & Spending

Distribution of Medicaid Spending

Medicaid Expansion Status

KFF, Status of State Medicaid Expansion Decisions, 2026.

Uninsured Rate

State Health Facts, Uninsured Rates for People Ages 0-64 by Age, 2024.

Demographic Characteristics of Medicaid Enrollees
Median Eligibility Levels

Status of State Medicaid Expansion Decisions

Published: Oct 16, 2026

The Affordable Care Act’s (ACA) Medicaid expansion expanded Medicaid coverage to nearly all adults with incomes up to 138% of the Federal Poverty Level ($21,597 for an individual in 2025) and provided states with an enhanced federal matching rate (FMAP) for their expansion populations.

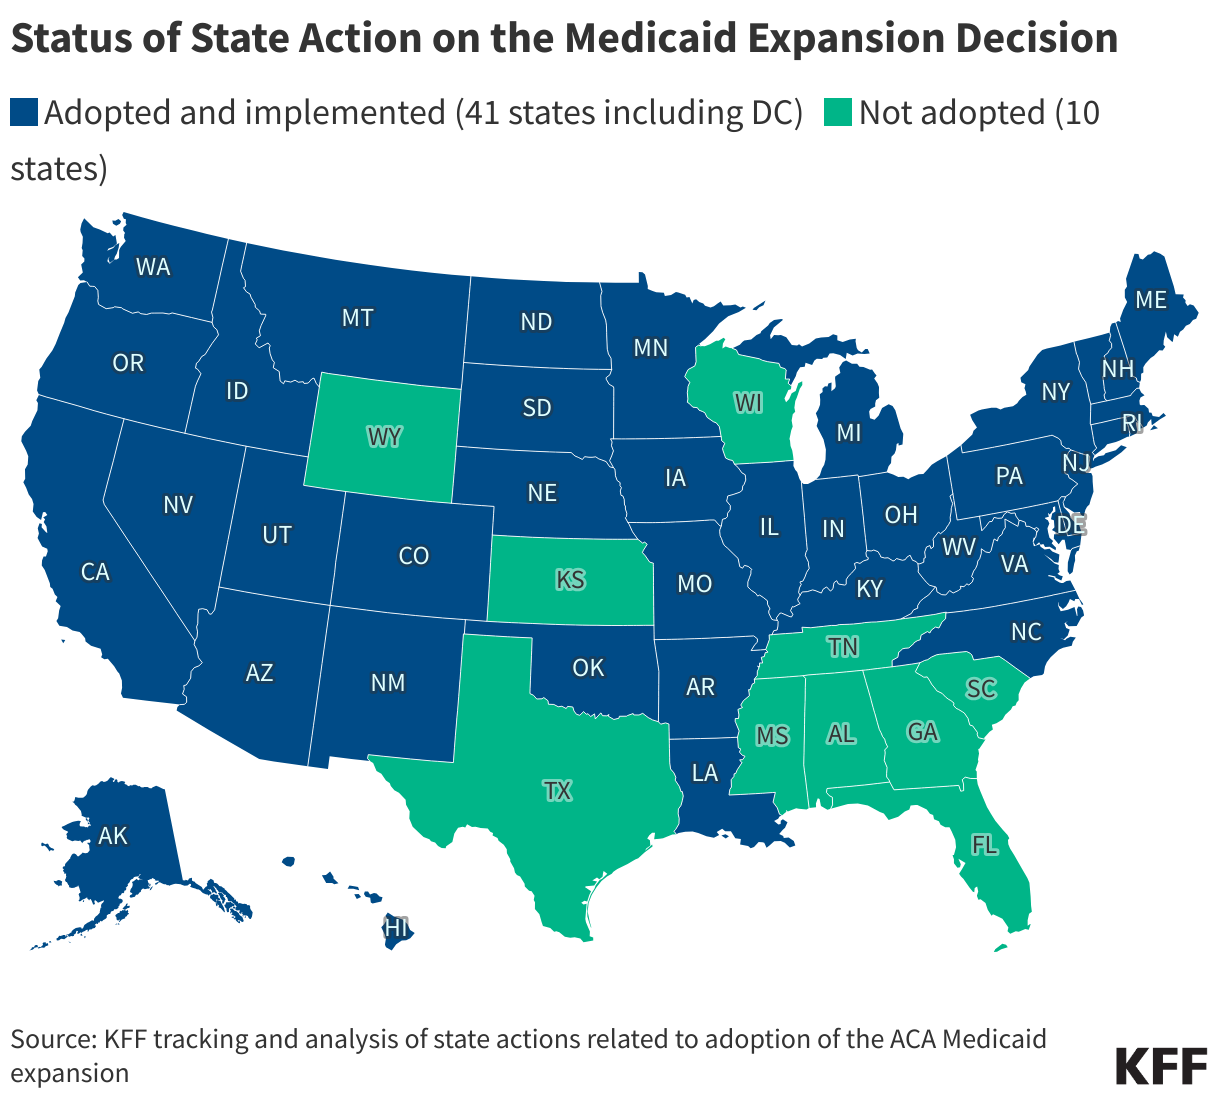
To date, 41 states (including DC)   have adopted   the Medicaid expansion and 10 states   have not adopted   the expansion. Current status for each state is based on KFF tracking and analysis of state expansion activity.

These data are also available in a table format. The map may be downloaded as a Powerpoint.

Status of State Action on the Medicaid Expansion Decision (Choropleth map)
Key States with Expansion Activity (Table)

Medicaid Expansion Resources

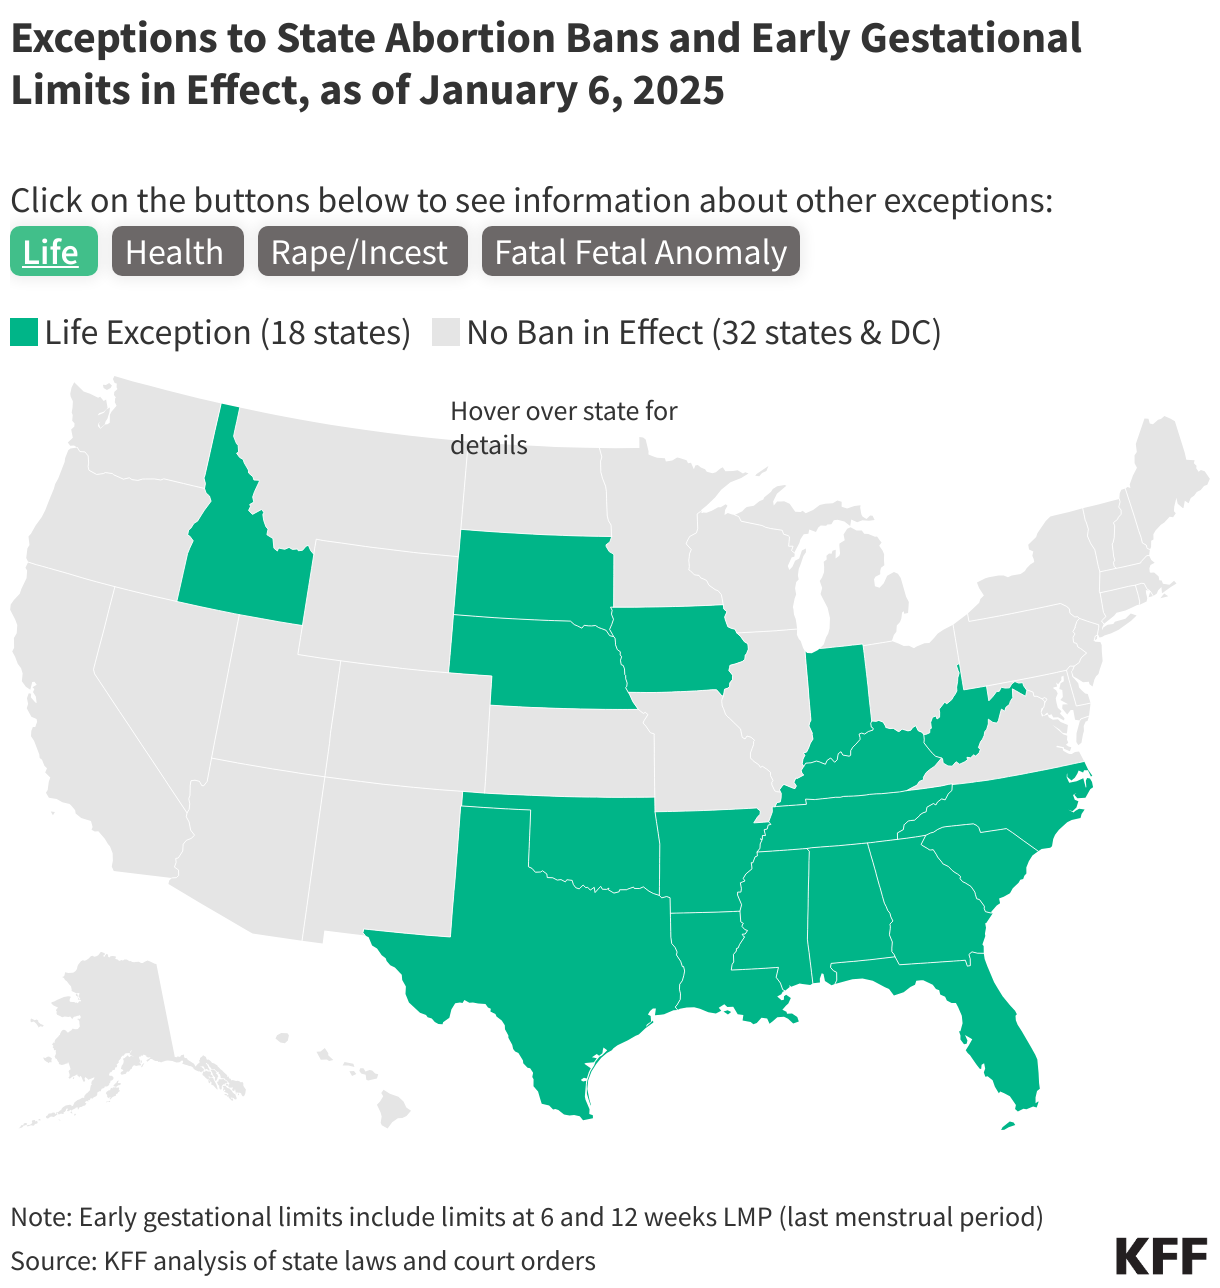
Policy Tracker: Exceptions to State Abortion Bans and Early Gestational Limits 

Last updated on October 16, 2026

states have abortion bans or early gestational limits in effect

states have no health exception

states have no rape or incest exception 

states have no fatal fetal anomaly exception 

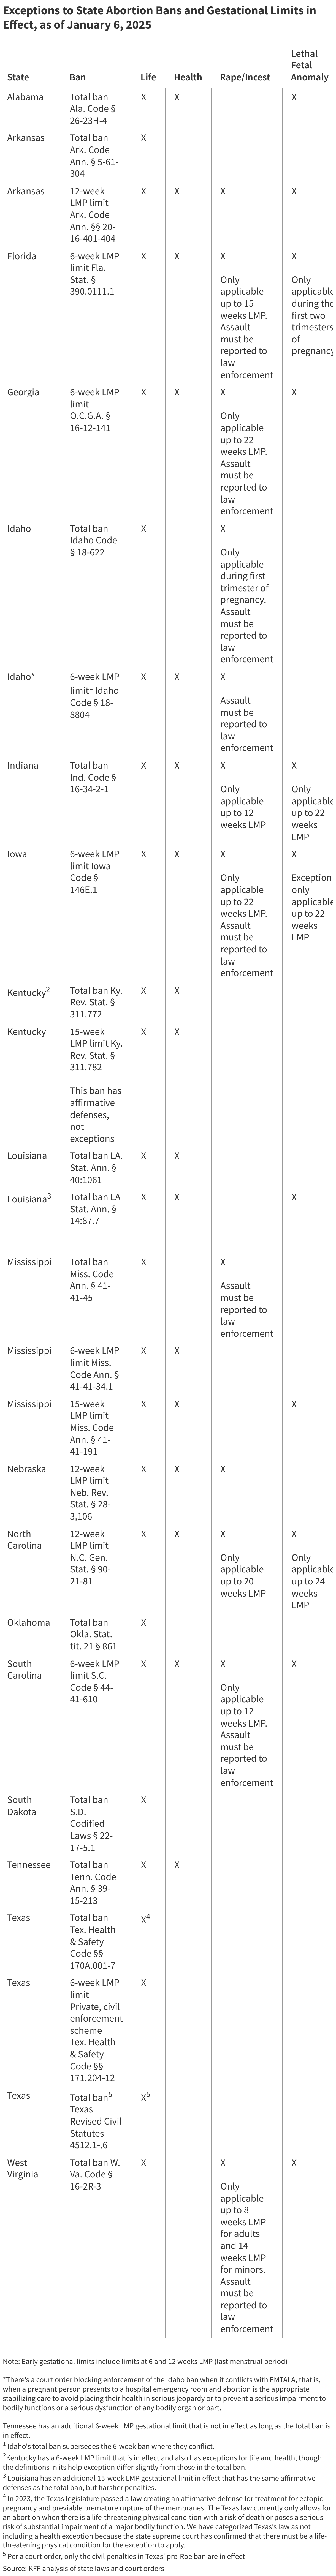
The provision of abortion is currently banned in 13 states and 6 states have early gestational limits between 6 weeks and 12 weeks in effect. Nearly all of these bans include exceptions, which generally fall into four categories: to prevent the death of the pregnant person, when there is risk to the health of the pregnant person, when the pregnancy is the result of rape or incest, and when there is a lethal fetal anomaly. Almost all states with a health exception limit it to conditions affecting physical health, with some going further by explicitly excluding emotional or psychological conditions. Alabama is currently the only state with an abortion ban or early gestational limit in place that includes an exception for mental health within its broader health exception. Some states have more than one abortion ban or restriction in place. The maps below illustrate the exceptions in each state’s most restrictive gestational limit or total ban. For details hover over each state to read the rollover.  

For more information on the status of state abortion bans, please visit our Abortion in the United States Dashboard. 

Exceptions to State Abortion Bans and Early Gestational Limits in Effect, as of October 16, 2026 (Choropleth map)
Exceptions to State Abortion Bans and Gestational Limits in Effect, as of October 16, 2026 (Table)

Green Card Processing Backlogs for Refugees and Asylees Could Have Implications for Health Coverage and Care 

Published: Oct 15, 2026

Introduction

The 2025 reconciliation law eliminated access to federally funded health coverage for refugees and asylees without a green card as well as several other groups of lawfully present immigrants. Refugees and asylees can apply for Lawful Permanent Resident status (LPR status, or a green card) after one year in the country or one year after being granted asylum. Because the 2025 reconciliation law largely limits eligibility for federally funded coverage to lawfully present immigrants with LPR status, how quickly U.S. Citizenship and Immigration Services (USCIS) processes these applications directly affects whether refugees and asylees can keep or gain access to Medicaid, the Children’s Health Insurance Program (CHIP), subsidized Affordable Care Act (ACA) Marketplace, and Medicare coverage.

This data note highlights changes in green card (I-485) application processing for refugees and asylees between fiscal year (FY) 2021 and FY2025, as well as across the first three quarters of FY2025 to FY2026 (since FY2026 data are only available through the third quarter). It discusses the implications of these trends for access to federally funded health coverage following eligibility changes under the 2025 reconciliation law. It is based on KFF analysis of USCIS data.

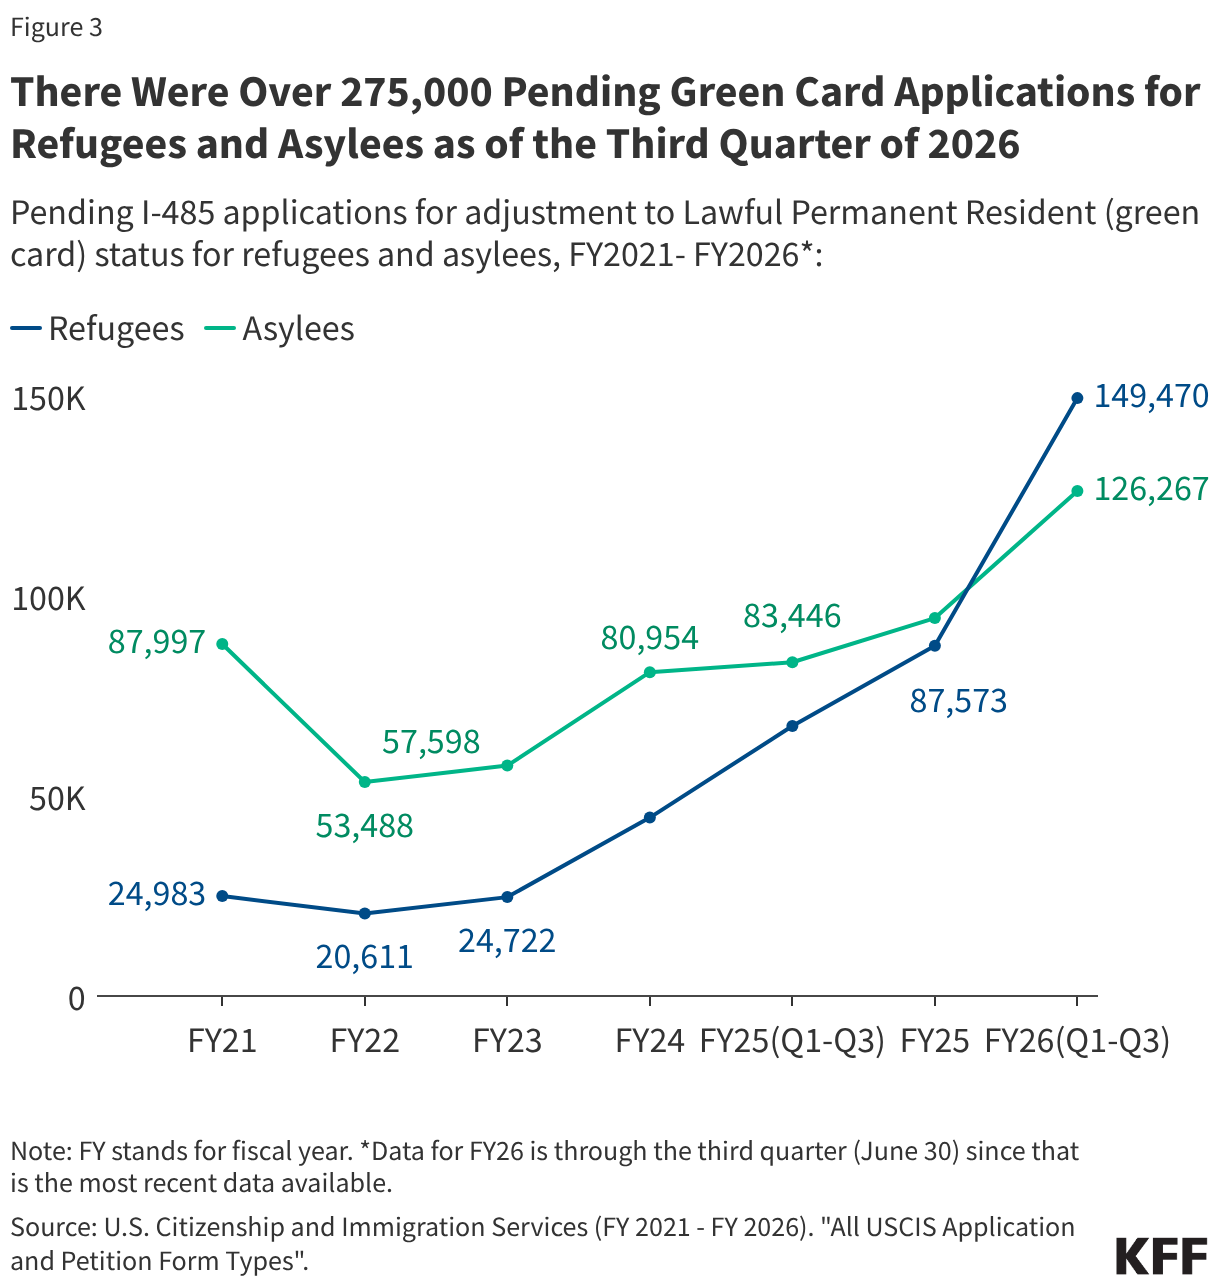
In this analysis, we find a decrease in USCIS completion of applications for adjustment to LPR status for refugees and asylees between FY2025 and FY2026. While some of the decreases in application completions could be due to fewer humanitarian migrants being admitted into the U.S. in recent years, we find that the number of applications completed by USCIS as a share of all applications fell between FY2025 and FY2026 and the average processing time for applications increased during the same time period. As of June 30, 2026, there were over 275,000 pending green card applications from refugees and asylees awaiting a decision from USCIS, and between FY2025 and FY2026, the average processing time for applications had increased from 7.8 months to 13.3 months for refugees and from 10.7 months to 19.9 months for asylees. As a result, many refugees and asylees who have already applied for a green card will be left without access to federally funded health coverage for potentially long periods of time as they wait for USCIS to process their green card applications.

Changes in Health Coverage for Refugees and Asylees

Since 1980, the U.S. has had a formal system for admitting refugees and asylees—individuals and their families who are unable to return to their country of nationality due to a well-founded fear of persecution for certain protected reasons. The right to seek asylum is rooted in international law, and the system reflects the U.S.’s longstanding inclusion of humanitarian protection as a core principle of immigration law. Refugees and asylees are generally fleeing from unsafe conditions and arrive to the U.S. with few to no resources, with many experiencing traumatic experiences in their countries of origin and/or during their journey to the U.S. The U.S. historically provided refugees and asylees access to assistance with food, housing, and health care upon arrival to the country as well as other time-limited services to support their transition to the U.S. Since taking office, the Trump administration has taken steps to significantly reduce the entry of refugees and asylees into the U.S., including by pausing refugee applications, setting the lowest ceiling for refugee admissions on record, and effectively closing the southern border to most migrants, including asylum seekers.

 Under federal law, refugees and asylees (i.e. those who have officially been granted asylum) can apply for adjustment to LPR status once they have been physically present in the U.S. for at least one year. They apply by filling out Form I-485, “Application to Register Permanent Residence or Adjust Status.” Asylum seekers whose asylum applications are still awaiting approval are not considered asylees and are not eligible to apply for LPR status regardless of their length of stay in the country.

The 2025 reconciliation law eliminated refugees’ and asylees’ longstanding access to federally funded health coverage as well as other public assistance programs. Most lawfully present immigrants, including most LPRs, must wait five years after getting a “qualified” immigration status before they can enroll in federally funded coverage such as Medicaid and CHIP. Under longstanding policy, refugees and asylees previously were exempt from this waiting period if they met income and other state eligibility requirements. They could also enroll in subsidized ACA Marketplace coverage and Medicare if otherwise eligible. However, the 2025 reconciliation law eliminates eligibility for Medicaid and CHIP (except in states that use a Medicaid and/or CHIP option to cover lawfully residing children and pregnant people), subsidized Marketplace coverage, and Medicare for refugees and asylees without a green card, as well as certain other groups of lawfully present immigrants. The Medicaid and CHIP restrictions took effect October 1, 2026, with restrictions on subsidized Marketplace and Medicare coverage fully taking effect in January 2027. The Congressional Budget Office estimates that the law’s eligibility restrictions for lawfully present immigrants will lead to about 1.4 million people becoming uninsured by 2034.

The number of I-485 applications received for adjustment to LPR status for both refugees and asylees increased between FY2021 and FY2025, but applications received for asylees dropped between FY2025 and FY2026. Between FY2021 and FY2025, I-485 applications received for adjustment to LPR status increased by 274% (22,906 to 85,743) for refugees and by 68% (44,837 to 75,292) for asylees. Lower numbers of I-485 applications received from refugees and asylees in FY2021 could reflect COVID-19-related reductions in the entry of migrants into the U.S. Between the first three quarters of FY2025 and FY2026, I-485 applications received for refugees continued to increase but at a lower rate of about 10% (59,754 to 66,013) and decreased by about 32% (58,682 to 40,344) for asylees. This pattern could reflect that the Trump administration lowered the refugee admissions cap from 125,000 in FY2025 to 7,500 for FY2026. Additionally, the Biden and Trump administrations effectively closed the border to individuals seeking asylum starting in 2024.

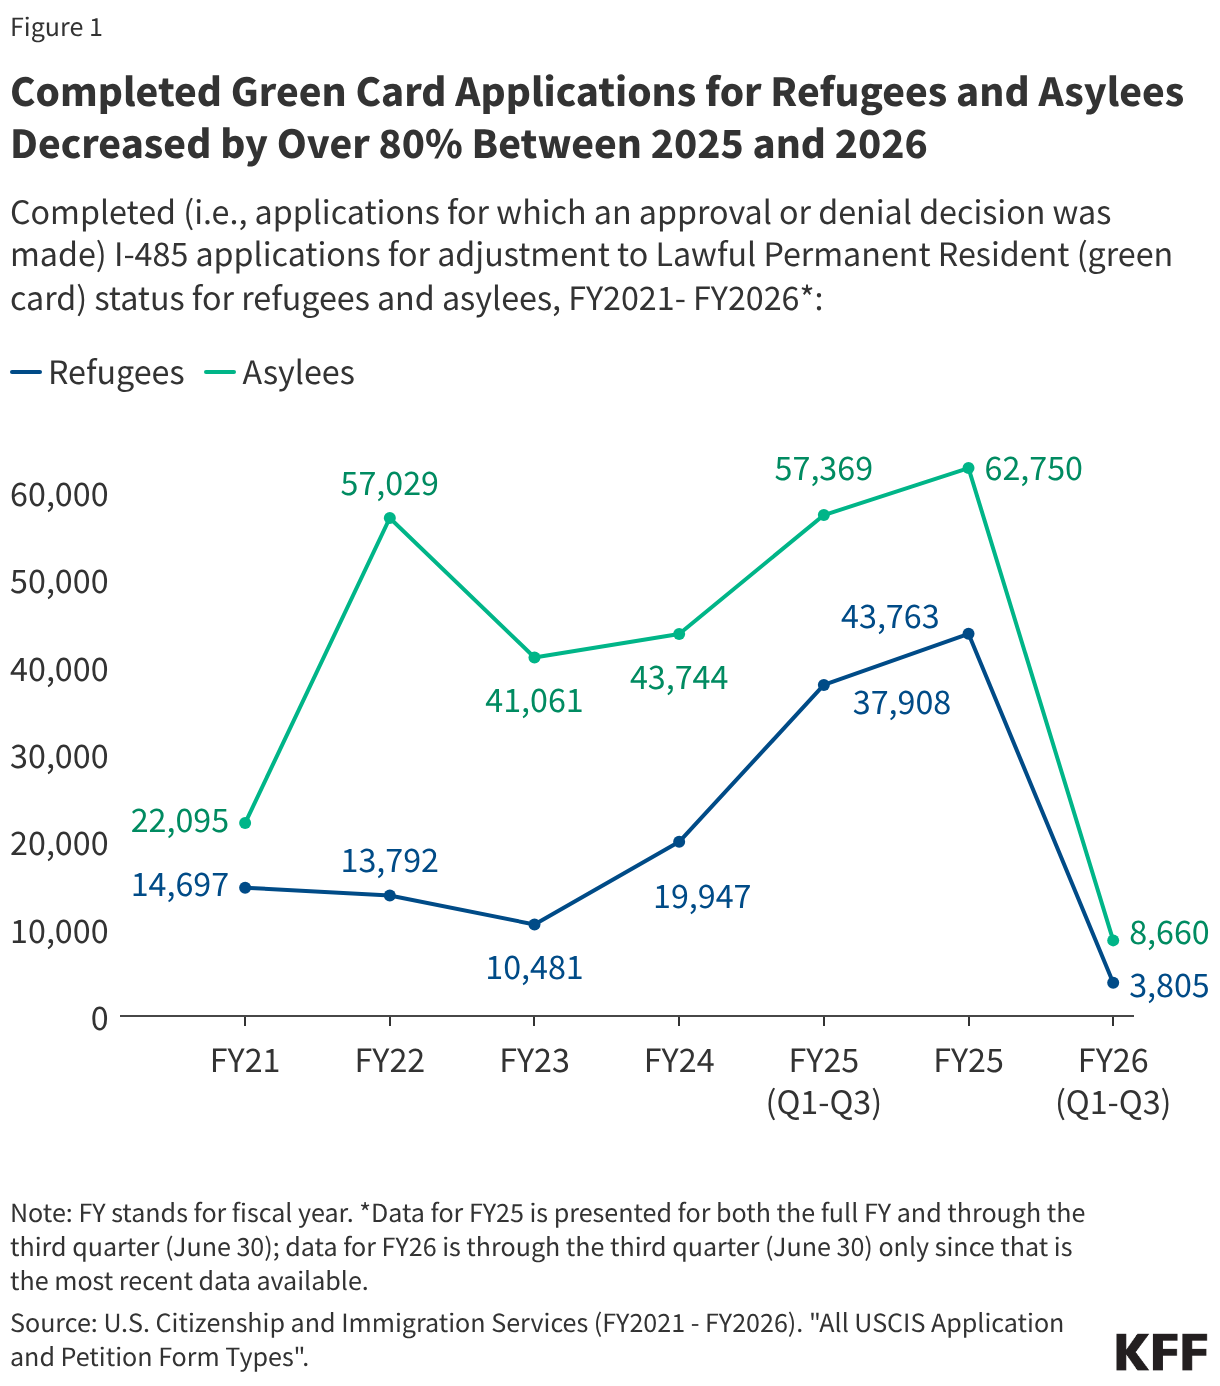
While the number of applications completed by USCIS for both refugees and asylees increased between FY2021 and FY2025, they decreased significantly between FY2025 and FY2026 (Figure 1). Between FY2021 and FY2025, completed I-485 applications, i.e., applications for which an approval or denial decision was made by USCIS, increased by 198% for refugees (14,697 to 43,763) and by 184% for asylees (22,095 to 62,750). However, between the first three quarters of FY2025 and FY2026, I-485 applications completed by USCIS decreased by about 90% (37,908 to 3,805) for refugees and by about 85% (57,369 to 8,660) for asylees.

Completed Green Card Applications for Refugees and Asylees Decreased by Over 80% Between 2025 and 2026 (Line chart)

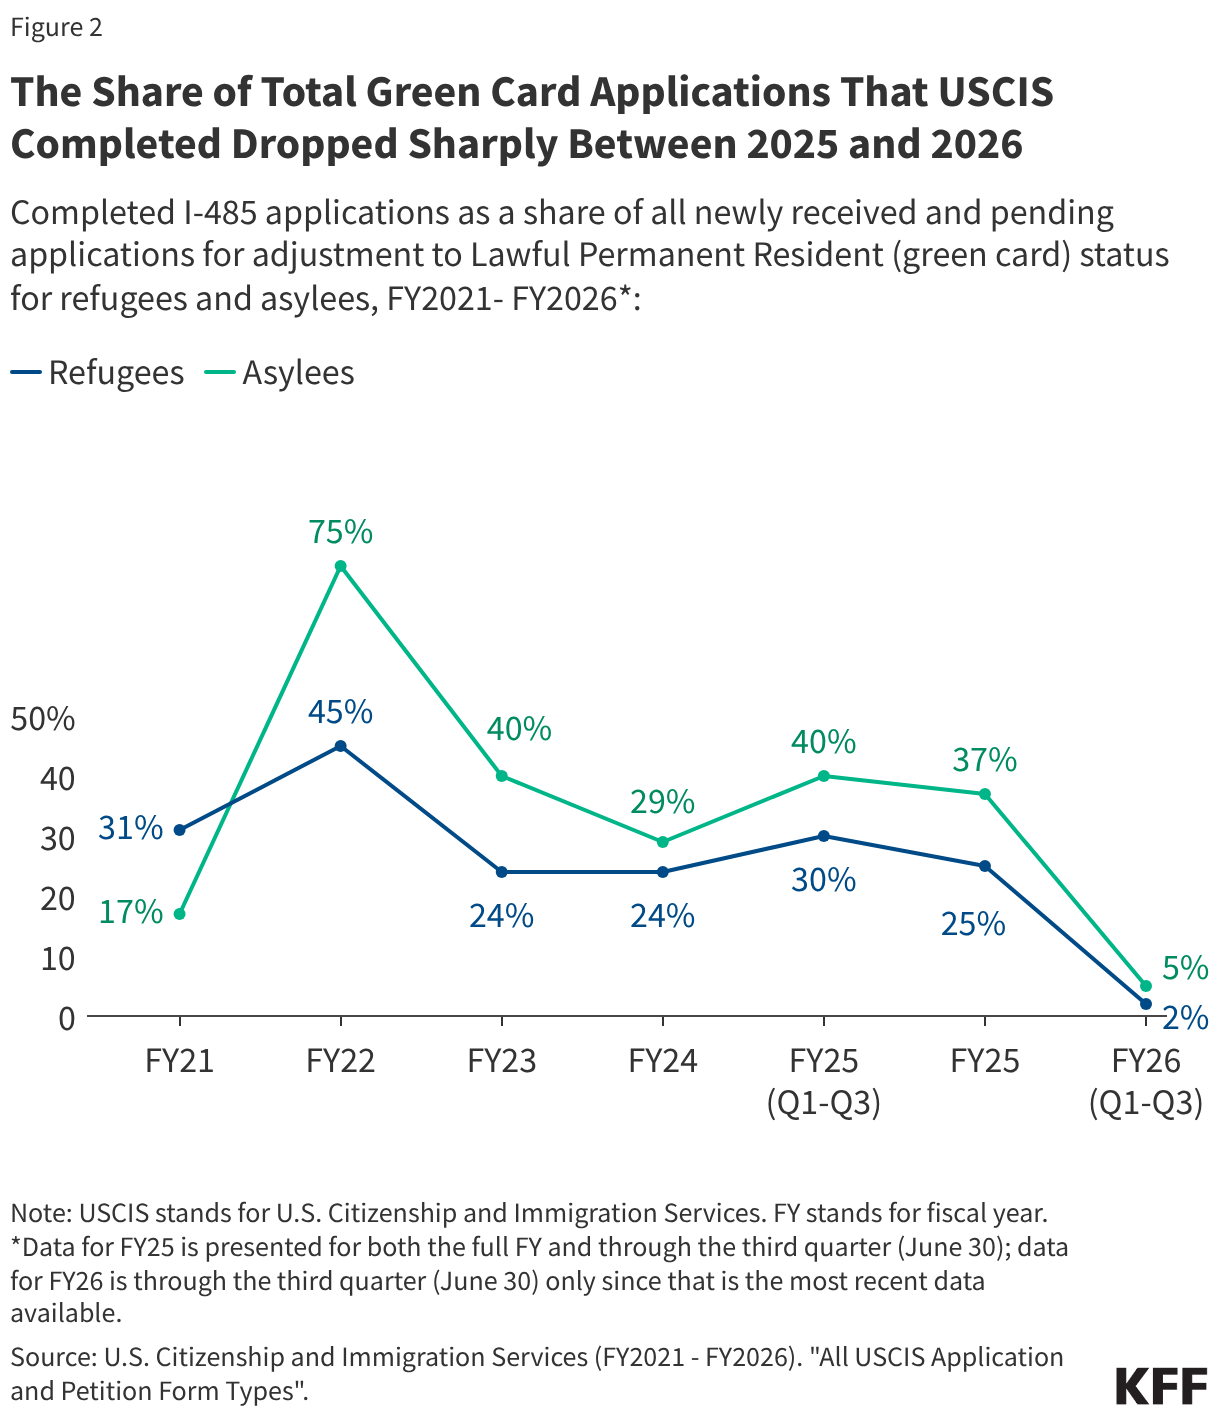
The percentage of completed applications as a share of all applications for refugees and asylees dropped sharply between FY2025 and FY2026 (Figure 2). Between FY2021 and FY2025, the percentage of I-485 applications completed by USCIS as a share of all applications (i.e., newly received and pending applications) decreased from 31% to 25% for refugees and increased from 17% to 37% for asylees. However, between the first three quarters of FY2025 and FY2026, completed I-485 applications as a share of all applications decreased sharply from 30% to just 2% for refugees and from 40% to just 5% for asylees.

The Share of Total Green Card Applications That USCIS Completed Dropped Sharply Between 2025 and 2026 (Line chart)

At the same time, the number of pending green card applications for refugees and asylees grew to over 275,000 as of the third quarter of FY2026, and application processing times increased between 2025 and 2026. The number of I-485 applications pending a decision from USCIS increased 251% for refugees, from 24,983 as of the end of FY2021 to 87,573 as of the end of FY2025, and by about 7% for asylees, from 87,997 as of the end of FY2021 to 94,482 as of the end FY2025 (Figure 3). Between the third quarter of FY2025 and the third quarter of FY2026, pending applications from refugees increased by 121% (67,502 to 149,470) and from asylees by 51% (83,446 to 126,267), for a total of 275,737 pending applications as of June 30, 2026. This number is expected to continue to increase by the end of FY2026. Further, reflecting the decrease in completed applications, the average processing time for green card applications increased from 7.8 months to 13.3 months for refugees, and from 10.7 months to 19.9 months for asylees between the first three quarters of FY2025 and FY2026. Within FY2026, the processing time for green card applications from refugees and asylees has increased each quarter, more than doubling from 7.6 months in Q1 to 17.6 months in Q3 for refugees and from 12.1 months in Q1 to 25.6 months in Q3 for asylees.

There Were Over 275,000 Pending Green Card Applications for Refugees and Asylees as of the Third Quarter of 2026 (Line chart)

Medicaid Waiver Tracker: Approved and Pending Section 1115 Waivers by State

Published: Oct 15, 2026

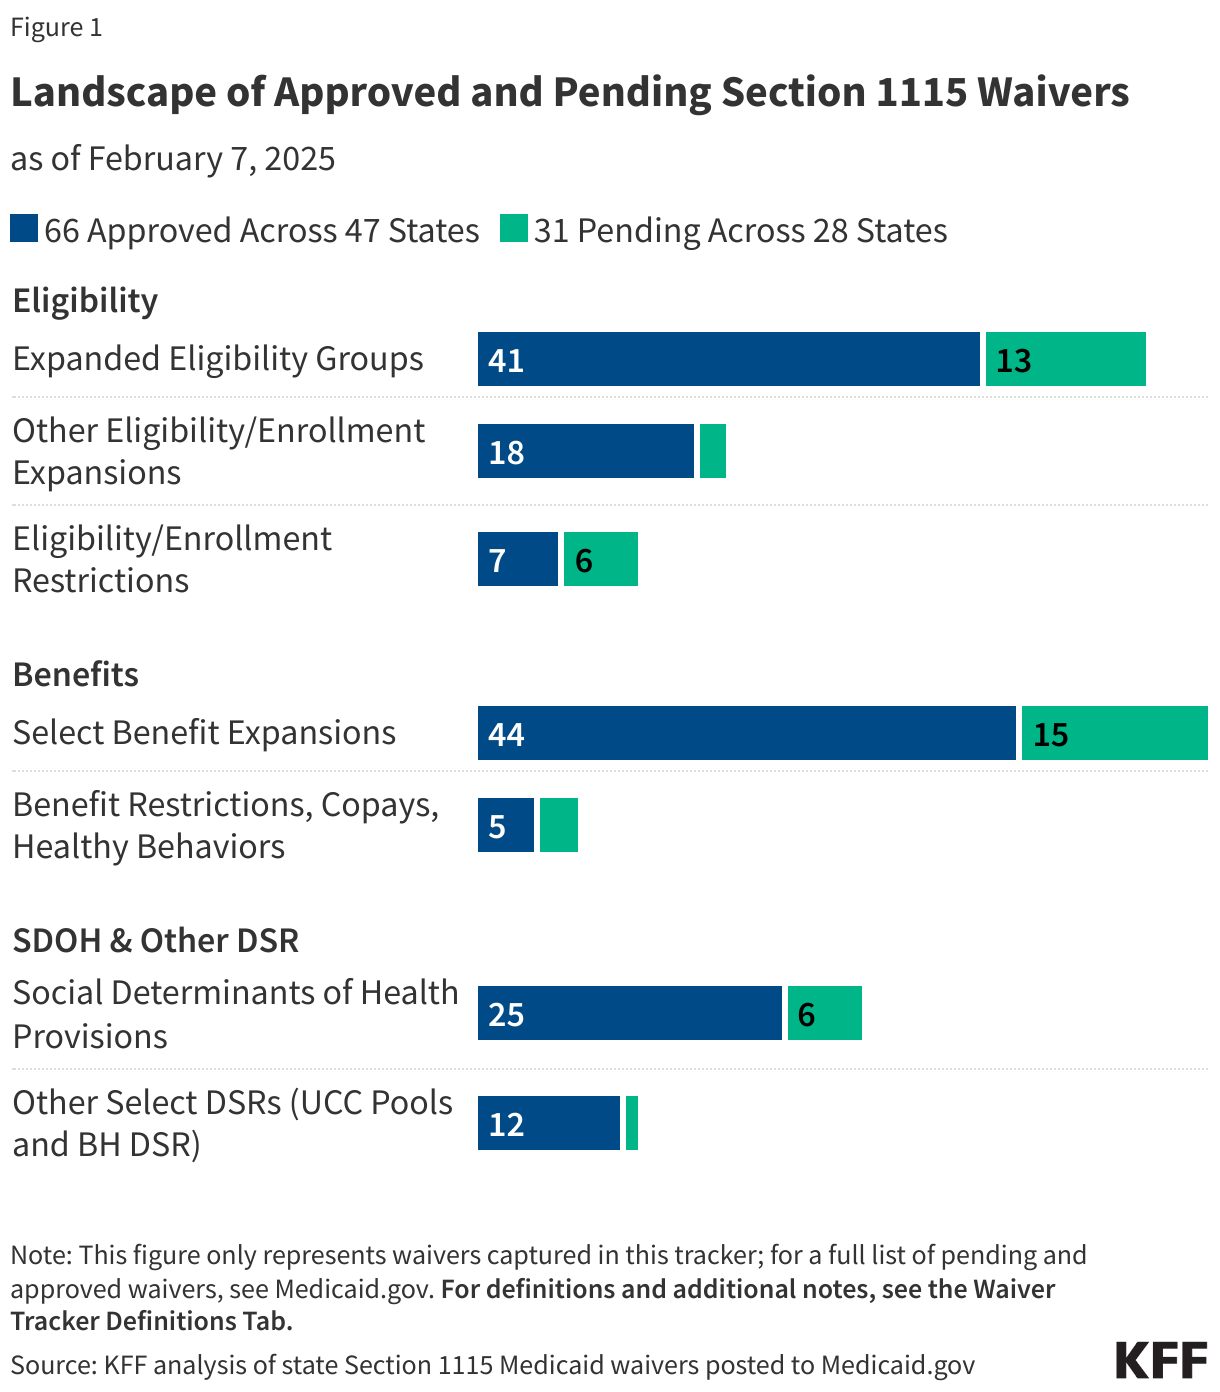
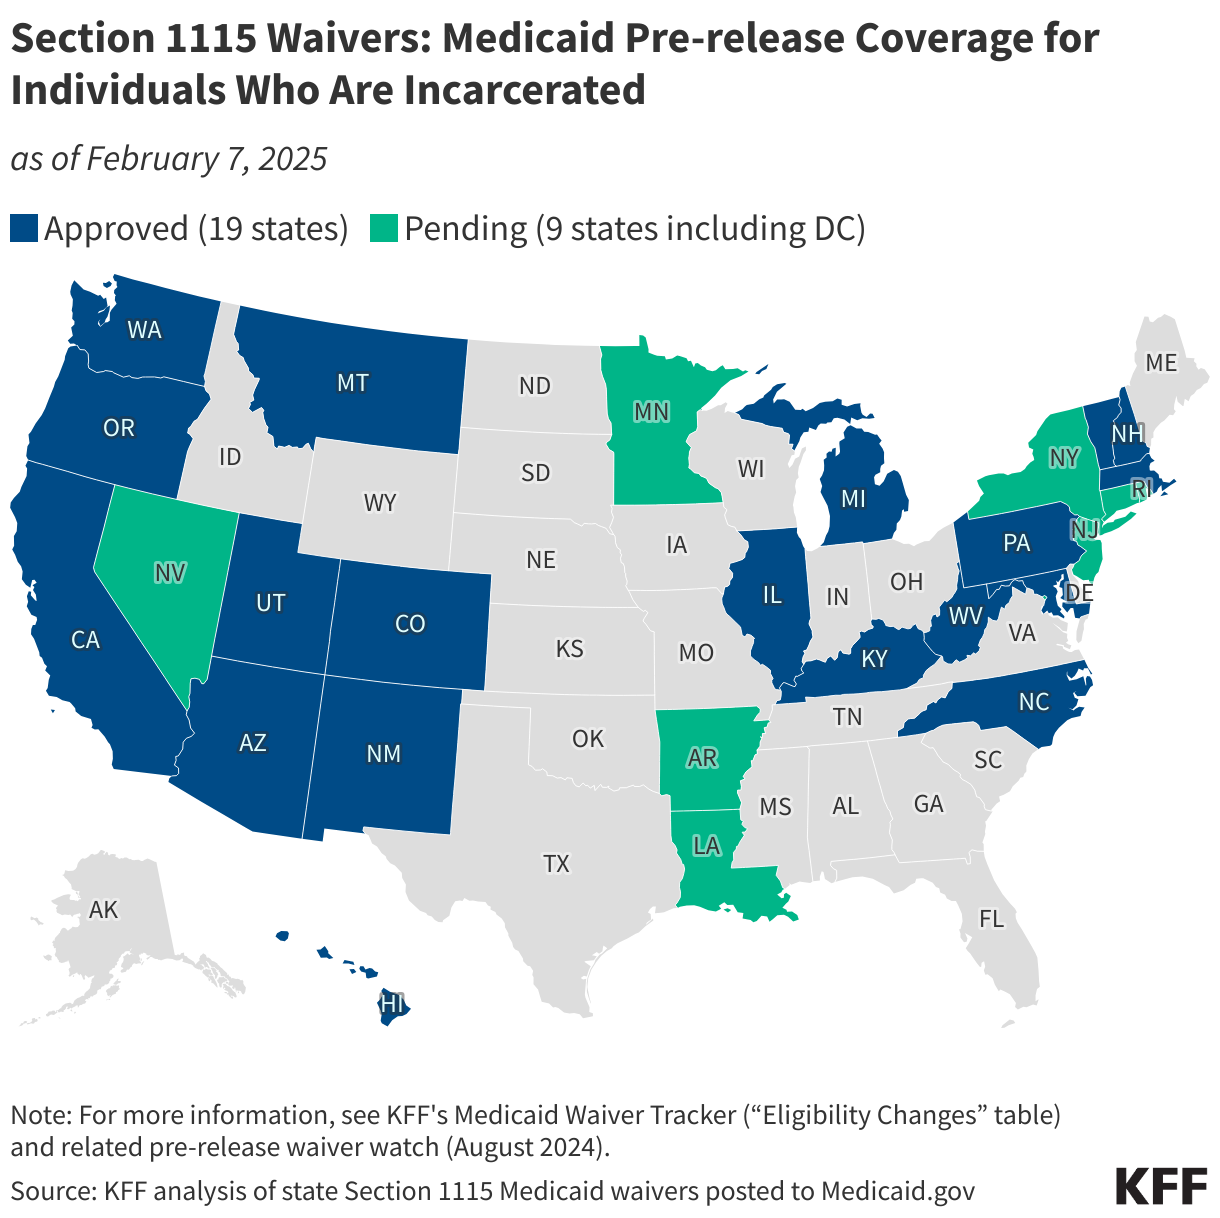
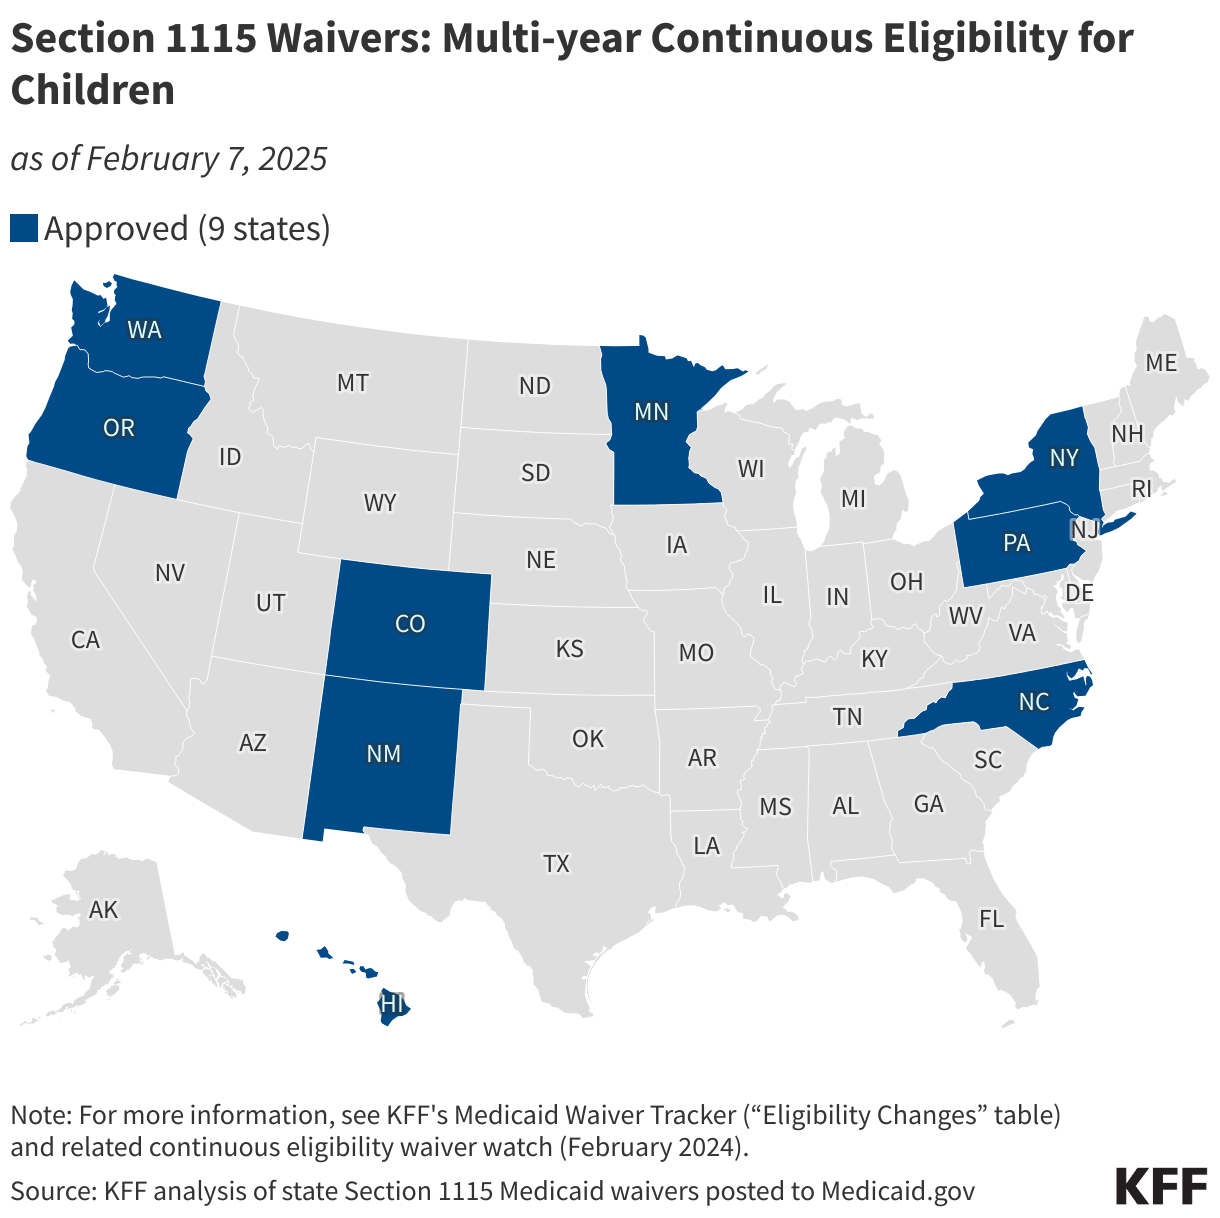
Section 1115 Medicaid demonstration waivers offer states an avenue to test new approaches in Medicaid that differ from what is required by federal statute, if [in the HHS Secretary’s view] the approach is likely to “promote the objectives of the Medicaid program.” They can provide states additional flexibility in how they operate their programs, beyond the considerable flexibility that is available under current law. Waivers generally reflect priorities identified by states as well as changing priorities from one presidential administration to another. Nearly all states have at least one active Section 1115 waiver and some states have multiple 1115 waivers. See the “Key Themes Maps” tab for a discussion of recent waiver trends.

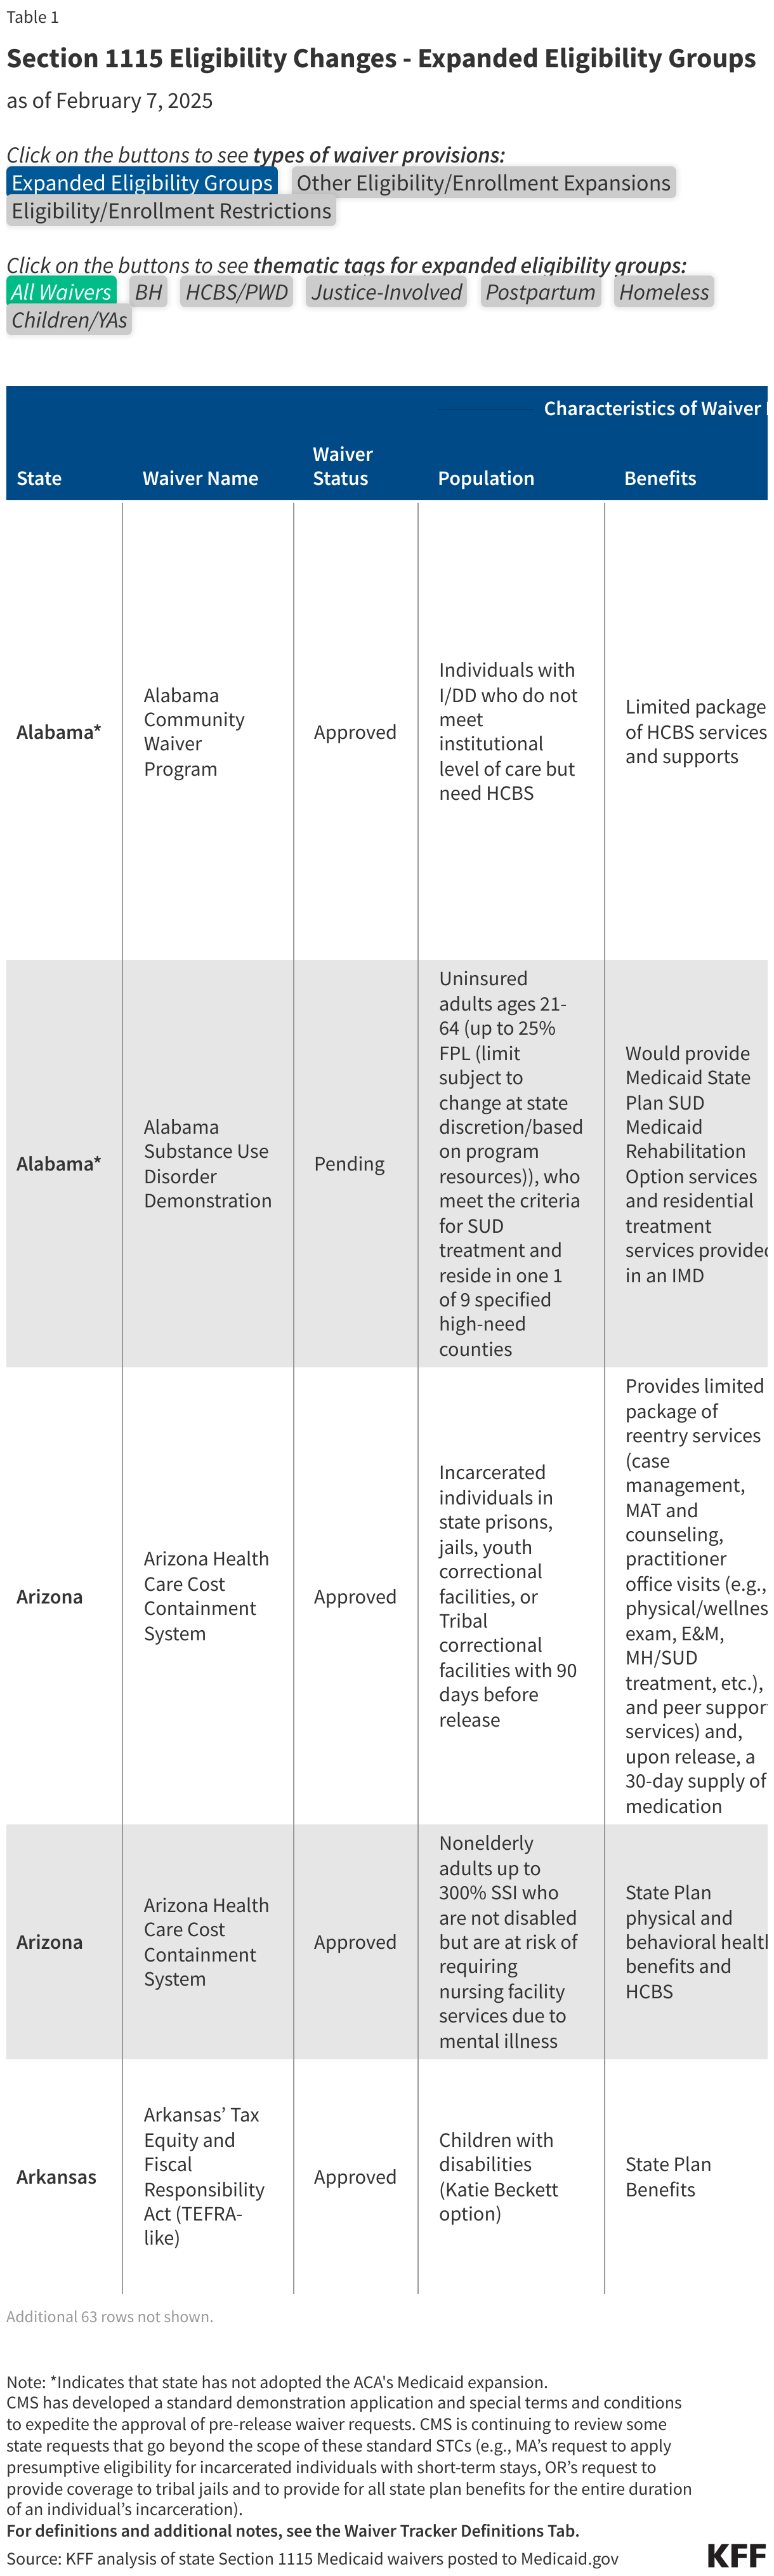
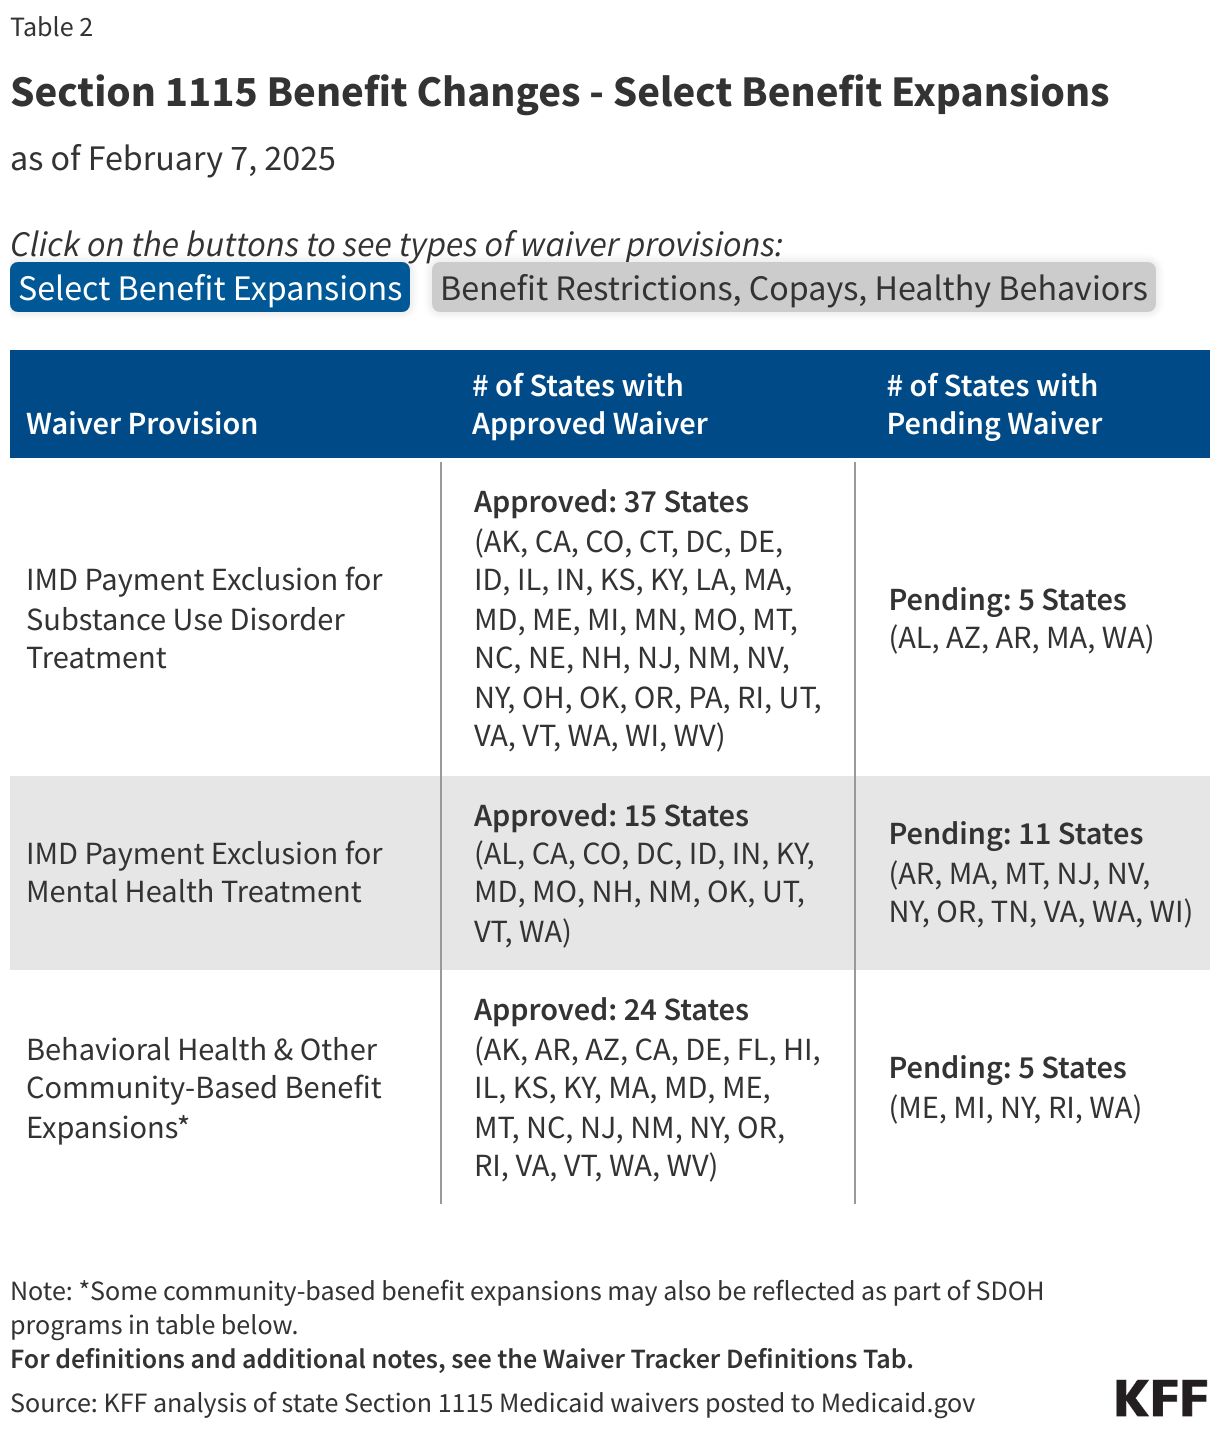
This page tracks approved and pending Section 1115 waiver provisions (including expansions and restrictions) related to eligibility, benefits, and social determinants of health and other delivery system reforms, once such waivers are posted to the state waivers list on Medicaid.gov. For more information on inclusion criteria and on each provision, as well as a list of acronyms, see the Definitions tab.

Landscape of Approved and Pending Section 1115 Waivers (Stacked Bars)


Waivers with Eligibility Changes

(back to top)

Section 1115 Eligibility Changes - Expanded Eligibility Groups (Table)

Waivers with Benefit Changes

(back to top)

Section 1115 Benefit Changes - Select Benefit Expansions (Table)

Waivers with SDOH & Other DSR Changes

(back to top)

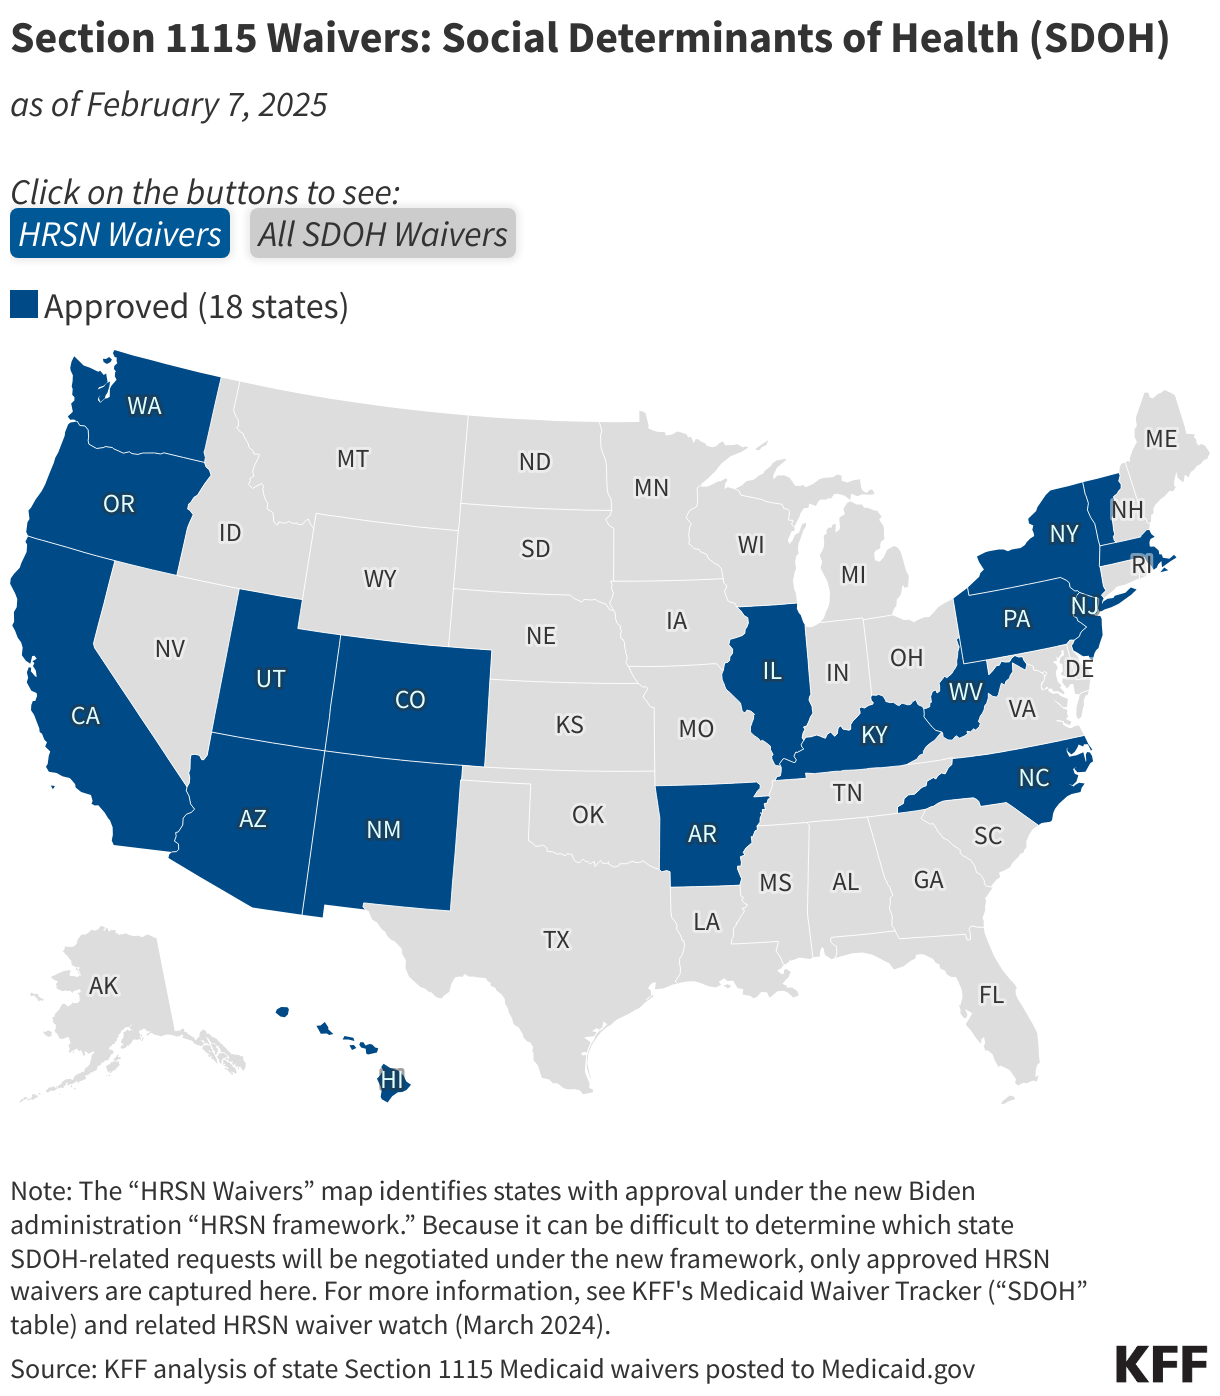
Section 1115 SDOH & Other DSR Changes - Approved SDOH Provisions (Table)

All Approved Waivers by Topic

(back to top)

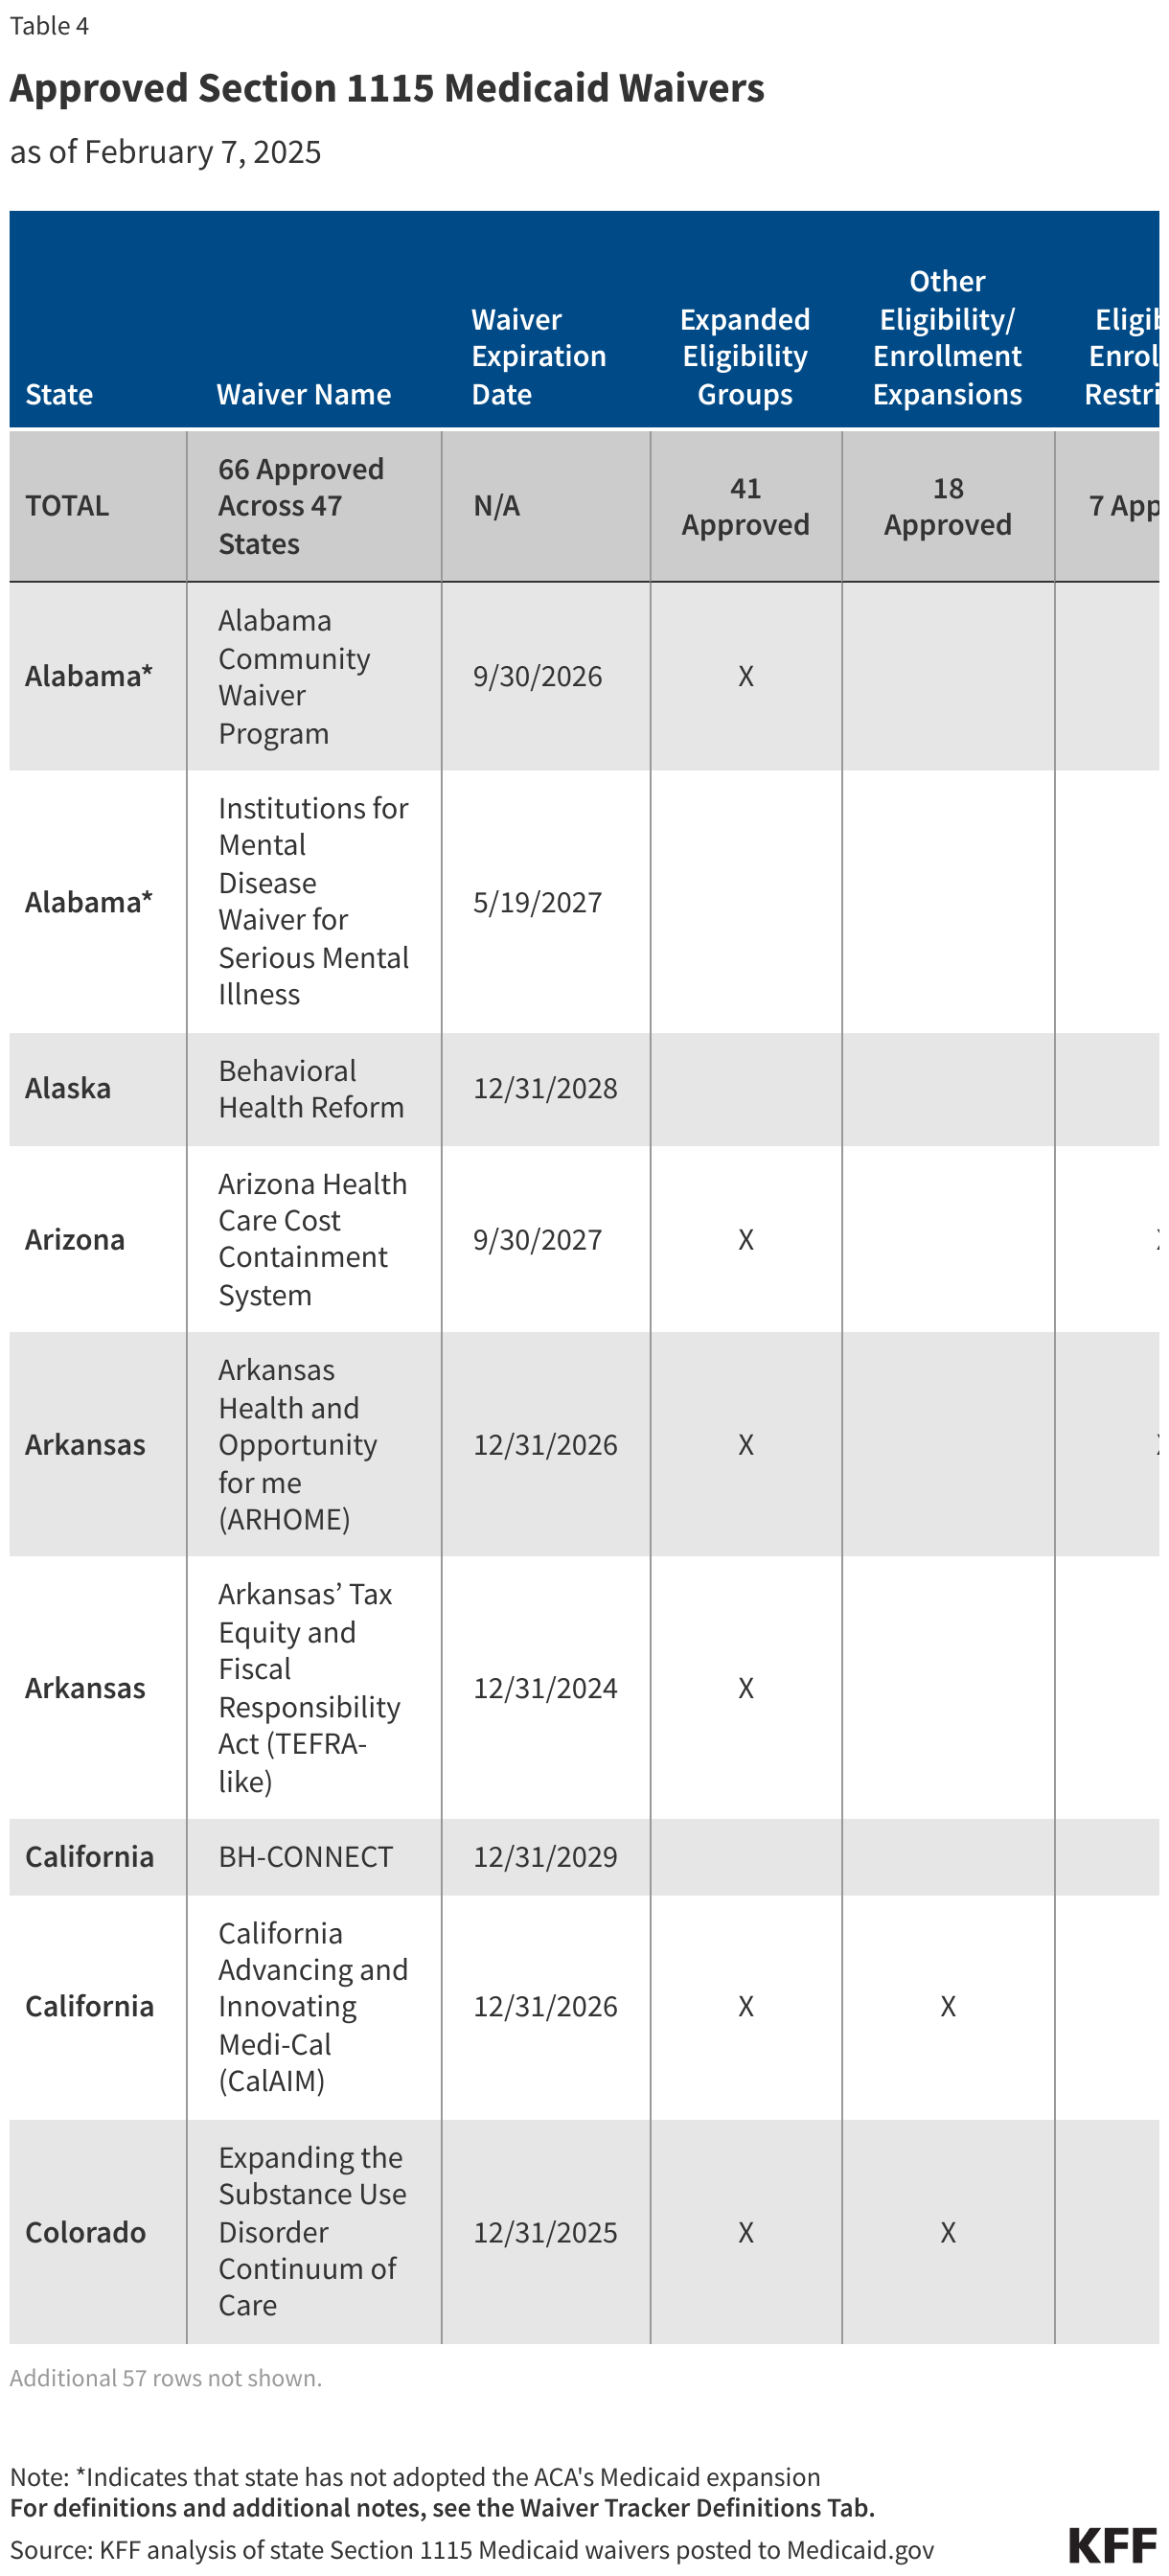
Approved Section 1115 Medicaid Waivers (Table)

All Pending Waivers by Topic

(back to top)

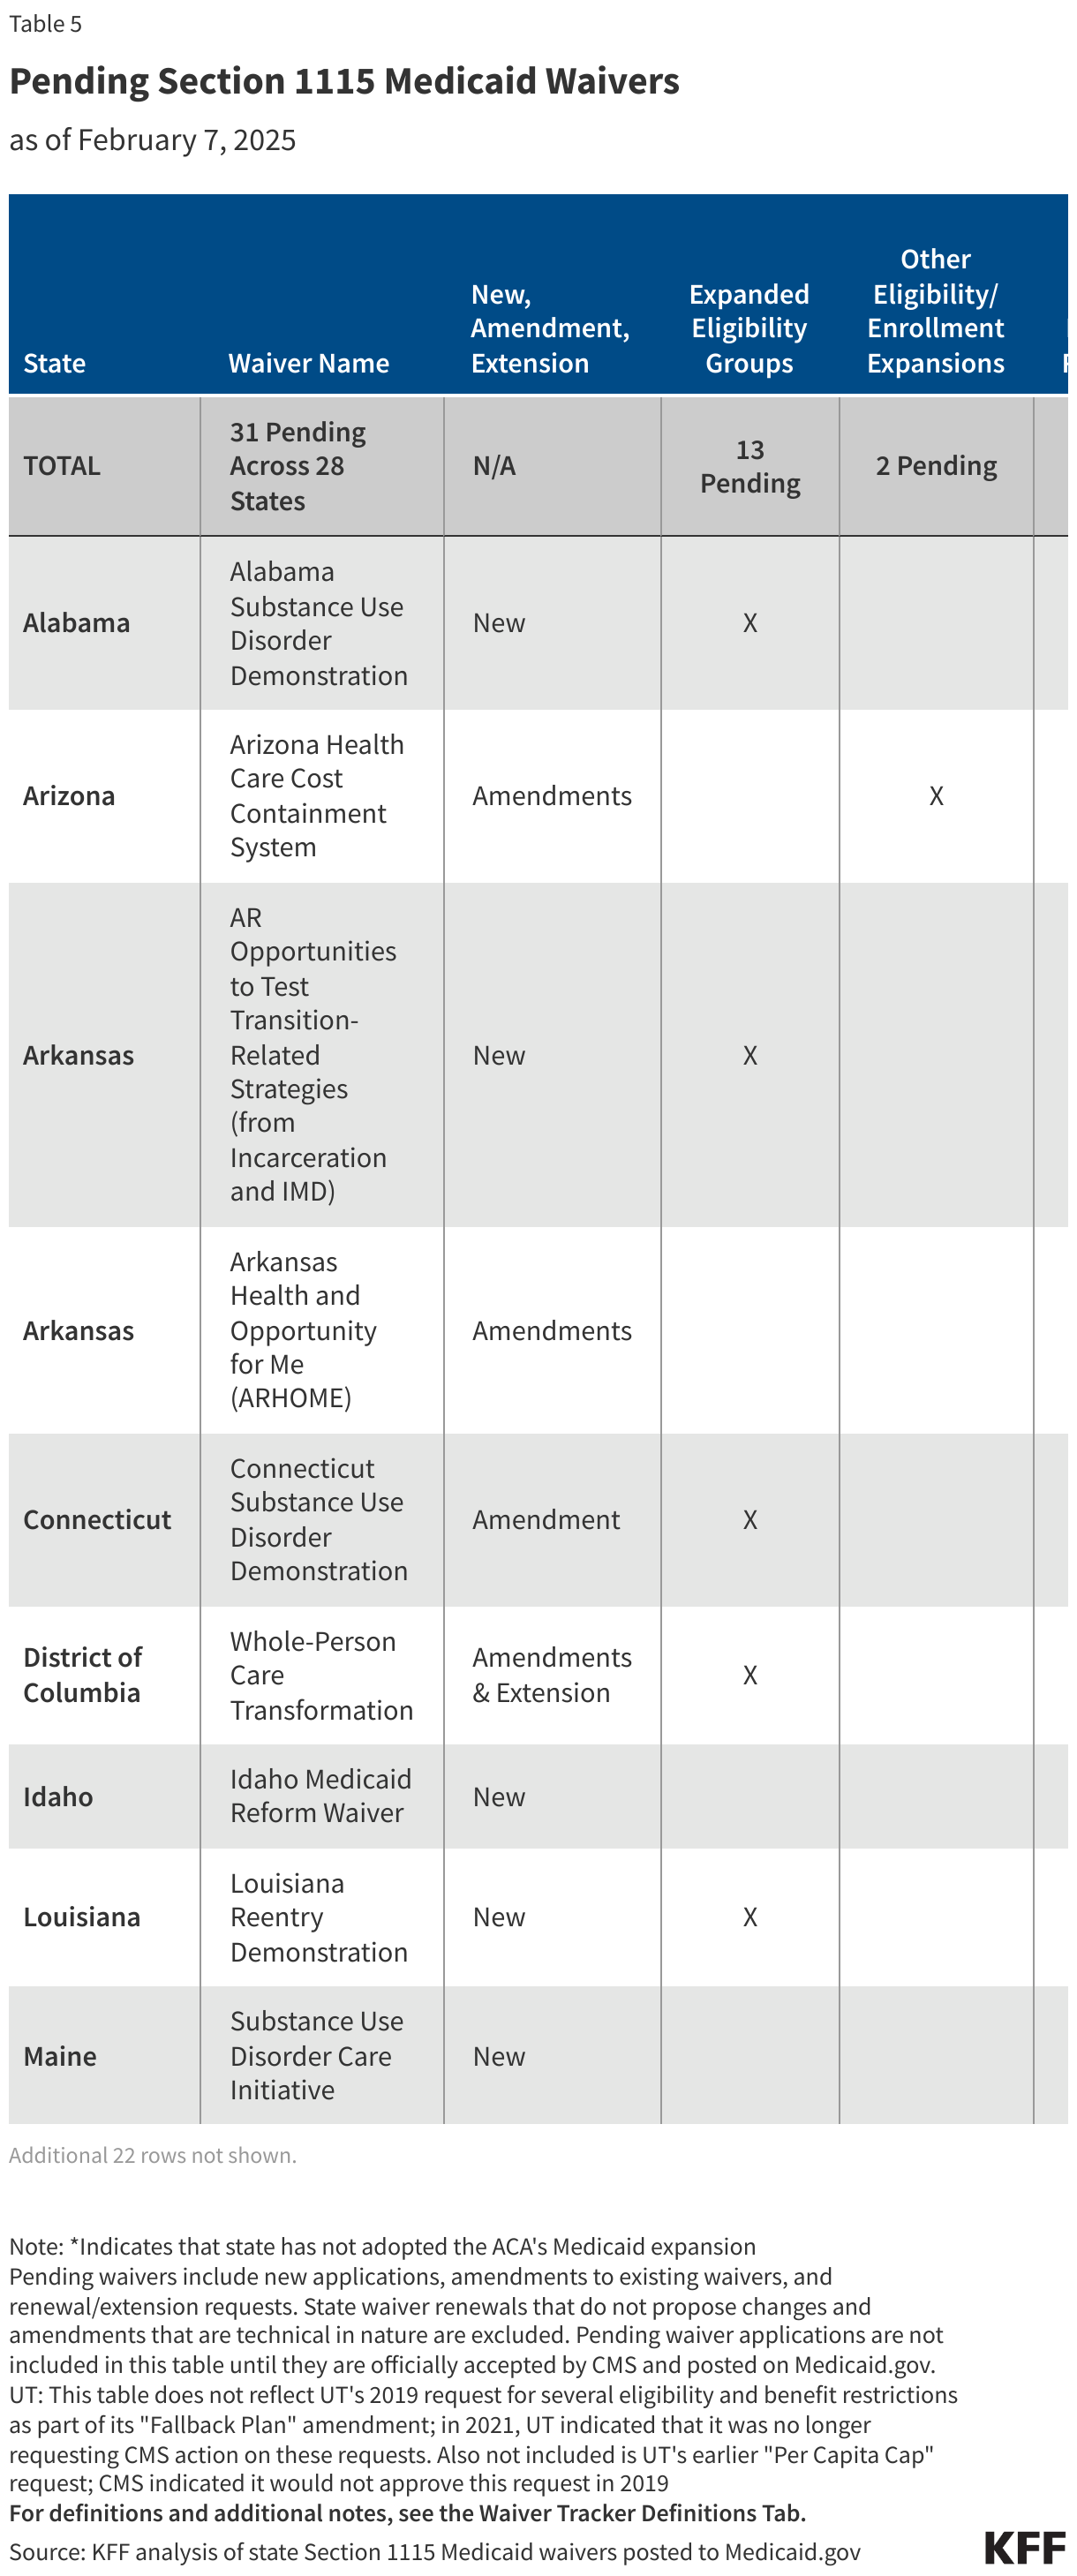
Pending Section 1115 Medicaid Waivers (Table)

See KFF's Work Requirements Tracker for additional state and national-level data related to work requirement implementation, including related KFF resources on work requirements.

The 2025 reconciliation law requires states to condition Medicaid eligibility for adults in the ACA Medicaid expansion group on meeting work requirements starting January 1, 2027; however, states have the option to implement requirements sooner through a state plan amendment (SPA) or through an approved 1115 waiver.

State Plan Amendments (SPAs)

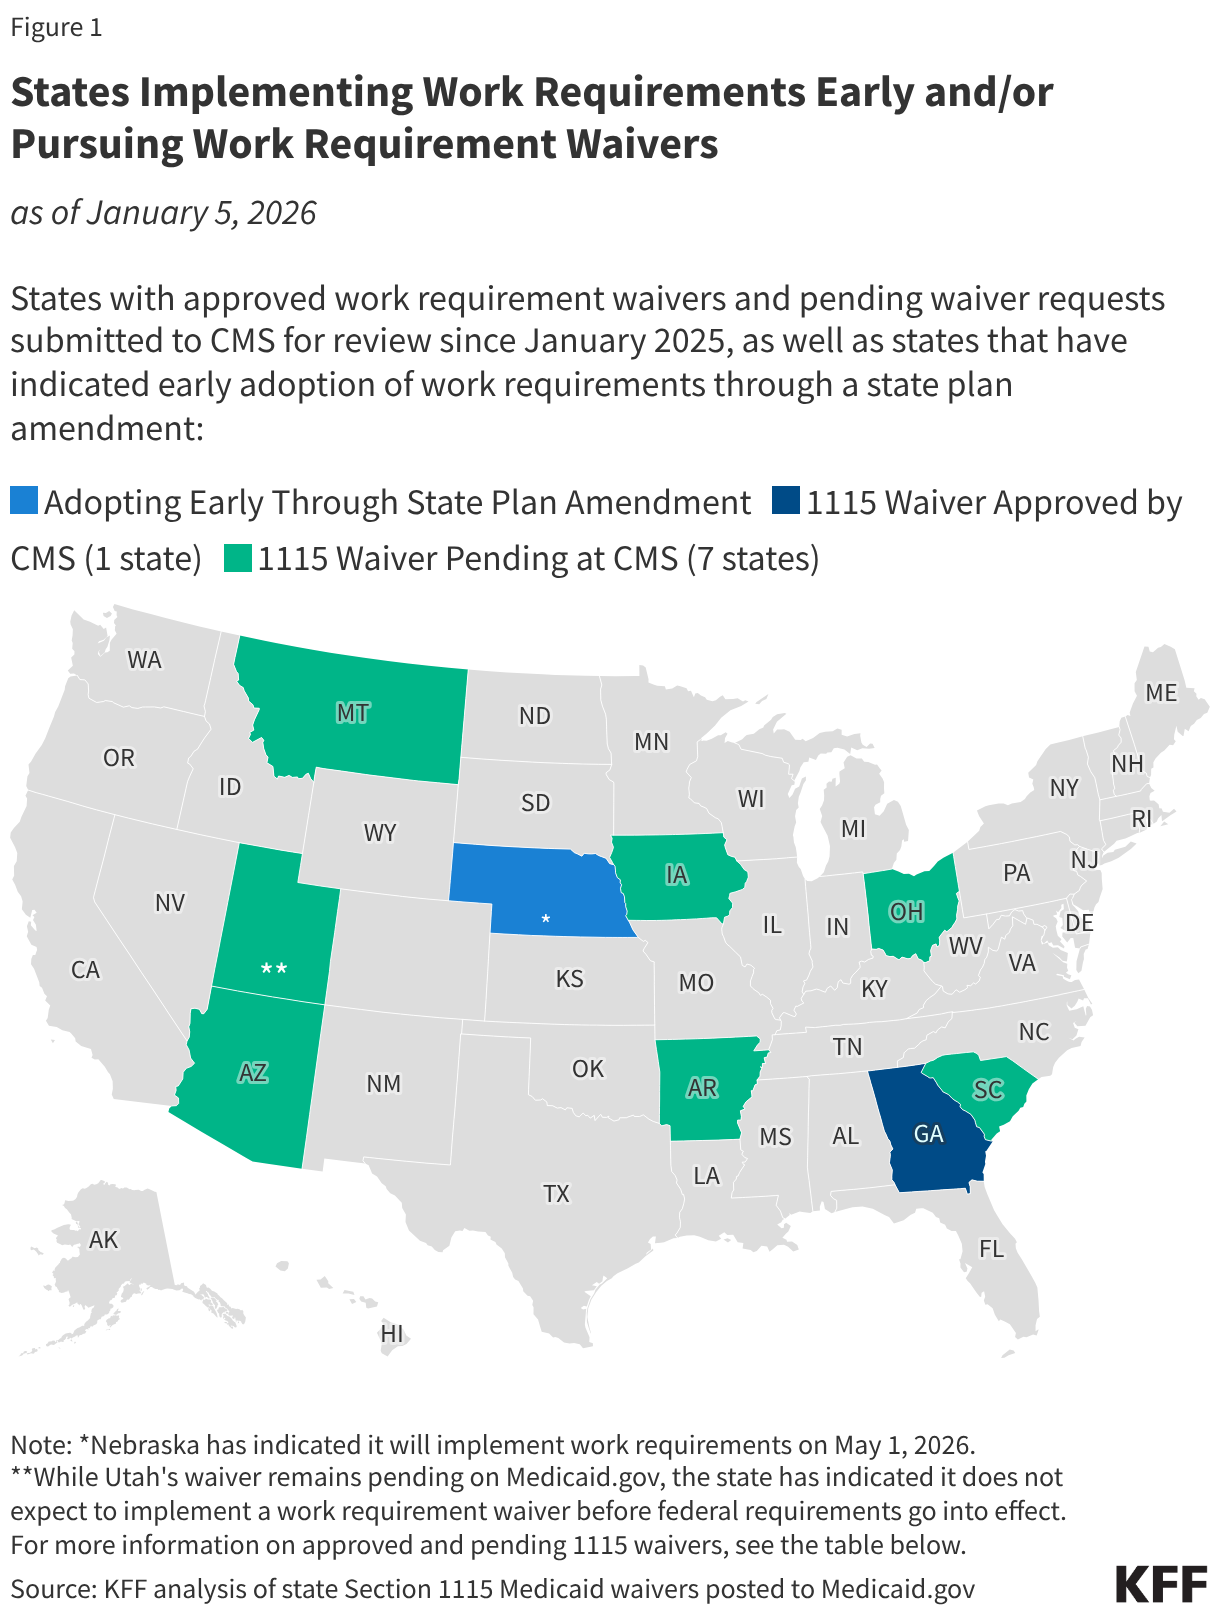
States may choose to implement work requirements prior to the required January 1, 2027 implementation date through a state plan amendment. Nebraska is the first state to announce that it will begin enforcing federal work requirements early through a state plan amendment, starting May 1, 2026. Two other states are also planning to implement before January 2027–Montana on July 1, 2026 and Iowa on December 1, 2026. Arkansas has announced that it plans to launch a soft implementation of work requirements on July 1, 2026 but will not disenroll individuals prior to January 1, 2027.

1115 Waivers

Since the start of the second Trump administration, several states have submitted waivers to implement work requirements. However, states are unlikely to be moving forward with proposed 1115 waivers at this time due to the passage of federal work requirements. States that plan to implement federal work requirements early will do so through a state plan amendment. Currently, Georgia is the only state with a Medicaid work requirement waiver in place following litigation over the Biden administration’s attempt to stop it. Georgia’s waiver will expire December 31, 2026; the state is required to come into compliance with the new federal requirements effective January 1, 2027.

Early Implementation and Waiver Status

The map below identifies states that have indicated they will implement work requirements early through a state plan amendment as well as approved (Georgia) and pending work requirement waivers (submitted to CMS since the start of the second Trump administration). The table below the map provides more detailed state waiver information.

States Implementing Work Requirements Early and/or Pursuing Work Requirement Waivers (Choropleth map)

States with Work Requirement Waiver Activity (Table)

Section 1115 waivers generally reflect priorities identified by states as well as changing priorities from one presidential administration to another.  Key Biden administration 1115 initiatives included waivers addressing enrollee health-related social needs (HRSN), pre-release coverage for individuals who are incarcerated, and multi-year continuous eligibility for children.

In March 2025, the Trump administration rescinded HRSN guidance issued by the Biden administration. CMS indicates this does not nullify existing HRSN 1115 approvals but going forward they will consider HRSN / SDOH requests on a case-by-case basis. In April 2025, the Trump administration announced it would be phasing out federal funding for “Designated State Health Programs” (DSHP) in waivers. In July 2025, the Trump administration released guidance indicating it will not approve (new) or extend (existing) continuous eligibility waivers for children or adults. CMS also announced in July it would be phasing out initiatives to strengthen the Medicaid workforce for primary care, behavioral health, dental, and home and community based services (not depicted in maps below).

This page tracks pending and approved waivers in key areas of recent state activity and will track Trump administration action in these areas going forward. Hover over individual states to display waiver expiration dates.

Social Determinants of Health

Social determinants of health (SDOH) are the conditions in which people are born, grow, live, work and age. SDOH include but are not limited to housing, food, education, employment, healthy behaviors, transportation, and personal safety. In 2022, CMS (under the Biden administration) announced a demonstration waiver opportunity to expand the tools available to states to address enrollee “health-related social needs” (or “HRSN”) including housing instability, homelessness, and nutrition insecurity, building on CMS’s 2021 guidance. In 2023, CMS issued a detailed Medicaid and CHIP HRSN Framework accompanied by an Informational Bulletin, which were updated in 2024.

In March 2025, the Trump administration rescinded the Biden administration HRSN guidance. CMS indicates this does not nullify existing HRSN approvals but going forward they will consider HRSN / SDOH requests on a case-by-case basis.

The “HRSN Waivers” map below identifies states with approval under the Biden administration HRSN framework. The “All SDOH Waivers” map identifies SDOH-related 1115 waivers more broadly, including those that pre-date or were approved outside of the HRSN framework. For more detailed waiver information, refer to KFF’s Medicaid Waiver Tracker (“SDOH” table) and HRSN waiver watch  (March 2024).

Section 1115 Waivers: Social Determinants of Health (SDOH) (Choropleth map)

Medicaid Pre-release Coverage for Individuals Who Are Incarcerated

In April 2023, the Biden administration released guidance encouraging states to apply for a new Section 1115 demonstration opportunity to test transition-related strategies to support community reentry for people who are incarcerated. This demonstration allows states a partial waiver of the inmate exclusion policy, which prohibits Medicaid from paying for services provided during incarceration (except for inpatient services). Reentry services aim to improve care transitions and increase continuity of health coverage, reduce disruptions in care, improve health outcomes, and reduce recidivism rates. The Biden administration approved 19 state waivers to facilitate reentry for individuals who are incarcerated. 

In September 2026, the Trump administration approved five reentry waivers and indicated that updated reentry demonstration guidance would be released within the next year. The map below identifies states with approved and pending waivers to provide pre-release services to Medicaid-eligible individuals who are incarcerated.  Medicaid pre-release waivers have been pursued by both Republican and Democratic governors. For more information, refer to KFF’s Medicaid Waiver Tracker (“Eligibility Changes” table) and related pre-release waiver watch (August 2024).

Section 1115 Waivers: Medicaid Pre-release Coverage for Individuals Who Are Incarcerated (Choropleth map)

Multi-year Continuous Eligibility for Children

The Consolidated Appropriations Act, 2023 required all states to implement 12-month continuous eligibility for children beginning on January 1, 2024. The Biden administration approved 9 waivers that allow states to provide multi-year continuous eligibility for children (e.g., from birth to age six). Continuous eligibility has been shown to reduce Medicaid disenrollment and “churn” rates (rates of individuals temporarily losing Medicaid coverage and then re-enrolling within a short period of time).

In July 2025, the Trump administration released guidance indicating it will not approve (new) or extend (existing) continuous eligibility waivers for children or adults. The map below displays states with waiver approval to provide multi-year continuous eligibility for children.  For more information, refer to KFF’s Medicaid Waiver Tracker (“Eligibility Changes” table) and related continuous eligibility waiver watch (February 2024).

Section 1115 Waivers: Multi-year Continuous Eligibility for Children (Choropleth map)
Section 1115 Waiver Tracker: Key Definitions and Notes (Table)

Recent Developments

General/Overview Resource

Eligibility and Enrollment Expansions

Eligibility and Enrollment Restrictions

Work Requirements:

Other:

Benefit Expansions

Benefit Restrictions, Copays, and Healthy Behaviors

Social Determinants of Health

Delivery System Reform

How Is The Federal Government Counting Measles Deaths?

Published: Oct 15, 2026

Originally published on October 1, 2026, this policy watch has been updated on October 15, 2026 to reflect additional developments and updated measles death reports from Pennsylvania.

Overview

Amid the largest U.S. measles epidemic in decades, and one that threatens the country’s measles elimination status, a controversy has emerged regarding how to count deaths from measles. From August through October 15th this year, Pennsylvania has reported a total of six measles deaths had occurred in the state but so far, the Centers for Disease Control and Prevention (CDC) has recognized only two these in its official measles statistics. CDC announced in early September that it would change how it counts measles deaths, no longer relying solely on reports from state health departments and instead looking to official death records as tracked by the National Center for Health Statistics (NCHS, a sub-agency within CDC). This new CDC policy of relying on NCHS-based mortality data to count measles deaths marks a departure from historical norms and processes that have accepted measles death reports from state health departments.

This Policy Watch reviews how measles deaths are typically determined, how these deaths are counted by the federal government and the role of two distinct but related federal public health surveillance systems at the center of the controversy – the CDC’s Nationally Notifiable Diseases Surveillance System (NNDSS) and NCHS’ National Vital Statistics System (NVSS). NNDSS and NVSS are separate public health surveillance systems with their own strengths and limitations: with NNDSS focused on real-time disease tracking that at times can also provide preliminary mortality information, while NVSS is focused on collecting longer-term, retrospective data on deaths and providing final determinations regarding the cause(s) of death though not necessarily designed for real-time tracking.  These two systems are complements, but one does not entirely replace the other.

Context

On August 25, Pennsylvania Governor Josh Shapiro held a press conference to announce that two deaths attributed to measles had occurred, the first such deaths in the state since 1992. As is standard protocol for cases of infectious diseases of national interest such as measles, the Pennsylvania Department of Health (PA DOH) also reported these as “measles-associated” deaths directly to CDC via the Nationally Notifiable Disease Surveillance System (NNDSS). PA DOH relied on pre-existing definitions for measles and for respiratory disease-associated mortality – which include clinical, laboratory, epidemiologic, and vital records criteria – in making the determination that these particular deaths were measles associated.

The Secretary of Health and Human Services (HHS) Robert F. Kennedy, Jr. initially objected to Pennsylvania’s classification of these deaths as measles-associated, saying Shapiro’s announcement was “premature” and suggesting the deaths “may even have been altogether fabricated.” CDC staff initially accepting the state’s death reports, though Kennedy later asked the CDC Director to remove any reference to those measles deaths on the CDC website. After the coroner in Lancaster County confirmed that measles was a contributing cause to the reported deaths, on September 4 Kennedy recognized measles as the cause for “only the second infant’s death” and stated: “The National Center for Health Statistics does not currently have any death records from 2026 that indicate measles is the underlying cause” but indicated CDC will update its measles death statistics upon receipt of such records. On September 14, a CDC spokesperson stated the agency had changed how it will count measles deaths in its official statistics, and going forward CDC would “report measles deaths if and when the National Center for Health Statistics reports measles as the underlying cause of death.”  The next day, PA DOH reported two additional measles-associated deaths, bringing the state’s own total to four. However, at present the CDC measles outbreak tally reports two deaths for 2026, with a note saying: “This number is subject to change; CDC will update its reporting as additional information becomes available and relevant reviews are completed.” On September 30, the Pennsylvania Department of Health confirmed a fifth death and a sixth death was announced by the Franklin County Coroner on October 12.

Two Systems with Different Purposes

The dispute around reporting measles deaths has brought new focus to two separate federal public health surveillance systems: the Nationally Notifiable Disease Surveillance System (NNDSS) and the National Vital Statistics System (NVSS). Each of these has a long history, dating back to the early 20th century, but serves different purposes. These systems are described below (see Table 1). 

Nationally Notifiable Disease Surveillance System (NNDSS): Timely Case Reporting

NNDSS is a collaboration between CDC and jurisdictions across the country that supports sharing and monitoring public health information for a set of diseases and conditions of national interest. NNDSS has roots extending to a system established in 1893 by Congress for jurisdictions to report cases of disease to the Surgeon General. Over time the system expanded, with responsibility for overseeing the system transferred to CDC in 1961. Local and state public health departments have the authority and responsibility to track cases of disease, typically through reporting from health care providers, laboratories, and other sources. In turn, jurisdictions then may provide case information to CDC through NNDSS. Key characteristics of NNDSS include:

  • A set of approximately 120 diseases and conditions that are designated by CDC as “nationally notifiable,” meaning the agency requests state and local health departments report to CDC when new cases of any of these conditions are identified. Measles is a nationally notifiable disease, and has been since 1912. Importantly, CDC cannot require jurisdictions to report case information, but all do, especially for high consequence infectious diseases such as measles. CDC itself says “since continuous endemic measles transmission has been eliminated, measles is an immediately notifiable disease.”
  • For each NNDSS disease or condition there is a pre-established definition that jurisdictions can consult to help determine if a notifiable case has occurred. These case definitions assure a level of standardization across jurisdictions. The definitions for nationally notifiable diseases are developed in collaboration with the Council of State and Territorial Epidemiologists (CSTE) and intermittently updated and refined. The current NNDSS case definition for measles dates to 2013.
  • Jurisdictions determine the extent of detail provided in their reports. Information shared through NNDSS is “de-identified” (i.e. with personally identifying information removed), but jurisdictions may include demographic, clinical, and epidemiologic characteristics and the course of clinical illness (including whether death occurred) in their case reports.
  • NNDSS reports can preliminarily indicate the cause of death in a particular case, but are not expected or designed to be a final determination. For this reason, Pennsylvania has reported the four deaths as being “measles-associated” rather than presenting a final determination of measles as the cause of death. The NNDSS definition for measles does not include specific guidance for when and how to report a death as being caused by measles infection, though CDC reports it is working with CSTE to update the definition “to promote consistent classification and reporting of measles deaths across jurisdictions.” 
  • A relative strength of NNDSS is the ability for rapid communication of case-level epidemiologic information between jurisdictions and the CDC, which can allow for near real-time tracking of outbreaks and disease trends. A limitation is that rapidly reported information may only be preliminary in nature, and case reports could be incomplete or lacking in detail.
Table 1
Characteristics of the CDC’s Nationally Notifiable Disease Surveillance System (NNDSS) Case Data and NCHS’ National Vital Statistics System (NVSS) Mortality Data
CharacteristicCDC – NNDSS Case DataNCHS – NVSS Mortality Data
Primary PurposeTimely tracking of cases of important diseases and conditions occurring nationwideComprehensive tracking of mortality statistics, including cause of death
Basic Unit of ReportingCases (such as cases of measles infection); can include associated clinical outcomes such as deathDeaths
Primary Data Source(s)Reports submitted by state/local departments of healthDeath certificate data from state/local vital statistics offices
Timing/speedNear real-time for high consequence infectious diseases such as measlesA lag of 3 months up to a year between deaths and release of data
Approach to Death AttributionPotential provisional attribution of death related to a case (e.g. “measles associated” death) as determined by a jurisdictional health department’s analysis of clinical, epidemiological, laboratory, and other criteriaCause of death must be determined by a licensed provider such as a physician/coroner, and attribution can incorporate multiple factors as contributing causes to death
Key Strengths Related to Reporting DeathsTimely data collection and analysis supports rapid response and ongoing tracking of public health threatsComprehensiveness and completeness of mortality data and causes of death
Key Limitations and Challenges Related Reporting DeathsReported death information is preliminary in nature and may require further investigation/confirmation; reporting is voluntary and may not be completeTime lag between deaths and data availability
Sources: CDC, NCHS, and KFF Analysis.

National Vital Statistics System (NVSS): Comprehensive Cause of Death Reporting

NVSS is the federal government’s primary mechanism for tracking mortality (and other vital statistics) data. The NVSS has roots going back to 1902, when Congress created a permanent Census Bureau and authorized the government to obtain copies of state vital records. By 1933, all states were required to record births and deaths and provide data to the Census Bureau. The NCHS was created in 1960, with responsibility for federal vital statistics transferred there.  The responsibility and legal authority for documenting births, deaths, and other vital statistics resides at the state and local level, but by statute NCHS has authority to collect and review these data – each state has a contract with NCHS that allows the federal government access to this information to produce national vital statistics. Key characteristics of NVSS include:

  • Housing the most complete set of data on deaths and births in the U.S. Death certificate information captured through NVSS is the most comprehensive source for mortality information nationally.
  • Death certificate information captured through NVSS is considered the benchmark for cause of death data. When completing a death certificate, a provider must include the best and final judgement on the proximate cause(s) of death as well as potential other factors that may have contributed to the death. Information from an autopsy, or laboratory and other test results may be included. Demographic details are also reported through the system such as age, sex, race/ethnicity, and education.
  • Nuances regarding a possible chain of events leading to a death and potentially multiple contributing factors can introduce complexity in cause of death determinations. Regarding the Pennsylvania cases, there has been some debate about measles being a primary cause of the deaths reported by the PA DOH, especially in relation to one of the initial reported deaths – a newborn infant that died from a lacerated spleen but was also positive for measles. 
  • State/local vital records offices are responsible for inspecting death certificates for timeliness, completeness, and accuracy of information, processing, and storing the records. Data files derived from these state/local records are then transmitted to NCHS.
  • NCHS reviews and processes vital statistics data and codes mortality statistics according to the current revision of the International Classification of Diseases (presently ICD-10, which the U.S. began to use in 1999). ICD-10 provides definitions and rules for selecting the underlying cause of death when generating vital statistics through NVSS. Typically, NVSS will release “provisional” cause of death data with a 3 to 9 month lag (depending on the cause of death), though full provisional data may take up to one a year to be released. Final cause of death data is made available after about two years. For example, the most recent NVSS provisional cause of death data are for 2025 while the most recent final cause of death data are from 2024. In special circumstances, provisional death data can become available even earlier – for example, during the COVID-19 pandemic NVSS provided updated COVID-19 related death statistics on a weekly basis.
  • A relative strength of the NVSS is its completeness and the comprehensiveness of its cause of death information. A relative weakness of the NVSS is the time lag between when deaths occur and the availability of cause of death data.