Who Are Direct Care Workers and How Might Federal Policy Changes Impact the Workforce?

Published: Jul 9, 2026

Long-term care (LTC) encompasses the broad range of paid and unpaid medical and personal care services that assist with activities of daily living (such as eating, bathing, and dressing) and instrumental activities of daily living (such as preparing meals, managing medication, and housekeeping). The Department of Health and Human Services (HHS) reports that after age 65, over half of people will at some point need help with at least two activities of daily living, over half will use paid LTC, and over one-third will use some nursing home care. People under 65 with disabilities also rely on LTC for assistance with activities of daily living and instrumental activities of daily living. Medicaid is the primary payer for long-term care (LTC), and KFF analysis of Medicaid claims data found that over half of people who used any Medicaid LTC were under 65. 

Direct care workers play a pivotal role in providing LTC services. They perform demanding, high-stress work for low wages and often no benefits. This has contributed to the long-standing shortages and high turnover rates among direct care workers in both home care and institutional care settings. Recent federal policy changes could further exacerbate the challenge of retaining and growing the workforce to care for the aging population. Specific policy changes that could exacerbate these challenges include the following.

  • Broad changes to Medicaid, including $911 billion in reductions to federal spending and Medicaid work requirements, could have implications for the direct care workforce given Medicaid’s outsized role in LTC spending and relatively high Medicaid coverage rates among direct care workers.
  • Direct care workers may also feel the impacts of recent changes in immigration policy. Three in ten direct care workers are immigrants, including naturalized citizens and noncitizens, who include lawfully present and undocumented immigrants. The Trump Administration’s intensified immigration enforcement and restrictive policies are deepening anxiety and fear among immigrants of all statuses and could contribute to reduced immigration in the future, which could exacerbate workforce shortages.
  • Two proposed rules from the Department of Labor may also have an impact on direct care workers. One rule would roll back minimum wage and overtime protections for home care workers. The other rule would make it easier for employers to classify direct care workers as independent contractors, which would strip them of some labor protections.
  • CMS has also delayed enforcement of a provision in the Medicaid Access Final Rule that would have required states to establish an advisory group to provide recommendations on direct care worker provider rates.

This analysis uses the 2024 American Community Survey (ACS) to provide an overview of demographic and socioeconomic characteristics of the direct care workforce, including home health aides, personal care aides, and nursing assistants who work in nursing facilities, residential care facilities, home health, and settings that provide nonresidential services for older adults and younger adults with disabilities (see Methods). 2024 ACS data was released in late 2025 and is the most recent data available. Other KFF analyses on the direct care workforce in nursing homes include RNs and LPNs (collectively referred to as “nurses”), but this analysis excludes nurses and only includes aides that assist older adults and people with disabilities with essential daily tasks. Nurses provide key services for older adults and younger people with disabilities who use long-term care services but are excluded from this analysis because they are socioeconomically and demographically different than aides. Key takeaways include:

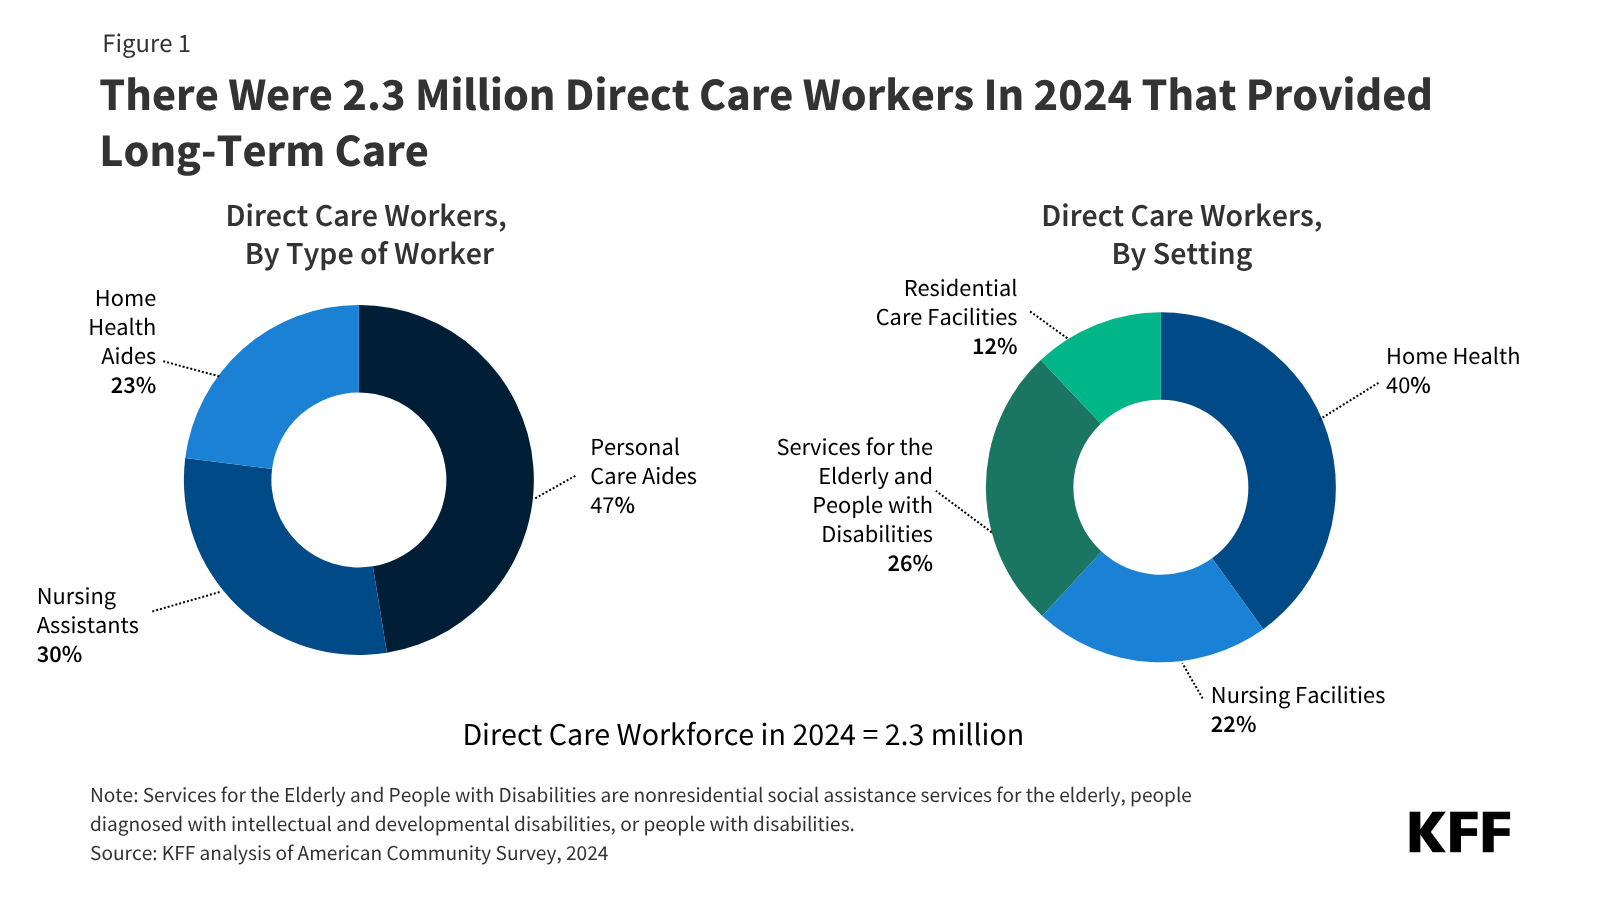
  • In 2024, there were 2.3 million direct care workers who provided long-term care to people ages 65 and older and people under 65 with disabilities (Figure 1).
  • Direct care workers are significantly more likely to be age 50 years or older, female, Black or Hispanic, or immigrants when compared to all other adult workers in the U.S. (Figure 2).
  • Direct care workers are also significantly more likely to have a high school degree or less, work part-time, be low-wage, or be covered by Medicaid or be uninsured when compared to all other adult workers in the U.S. (Figure 2).
  • The share of direct care workers who are immigrants varies by state, ranging from 0% in Wyoming to 60% in New York (Figure 4).
  • At least one in five immigrant direct care workers is from a country within the 75 countries that are part of the Trump administration’s immigrant visa pause, which could further strain the workforce in future years (Figure 5).

In 2024, there were 2.3 million direct care workers who provided long-term care to people ages 65 and older and people under 65 with disabilities (Figure 1). Direct care workers include personal care aides, nursing assistants, and home health aides.Other sources use a similar definition of direct care workers but use data from the Bureau of Labor Statistics (BLS) to estimate the total number of workers, leading to different counts. The BLS data are more recent than the American Community Survey. See Box 1 for a definition of types of direct care workers included in this analysis.

Direct care workers provide long-term care services across a variety of settings, with 66% providing care in home care settings, 22% in nursing facilities, and 12% in residential care facilities (Figure 1). “Home care settings” include “home health” and “services for the elderly and people with disabilities” from Figure 1 and Box 1. Excluding Figure 1 and Box 1, this analysis presents these categories as one combined “home care” category. See Box 1 for definitions of the direct care worker and setting types. 


Box 1: Who Are Direct Care Workers and Where Do They Work?

By Type of Worker:                                 

Personal Care Aides:Personal care aides assist older adults and people with disabilities living at home with ADLs. Personal care aides also help with instrumental activities of daily living (IADLs), such as grocery shopping, meal preparation, and managing medications.

Nursing Assistants: Nursing assistants, or certified nursing assistants (CNAs), typically work in nursing homes and assist residents with ADLs. All CNAs must have completed a nurse aide training and competency evaluation program within 4 months of their employment. They must also pursue continuing education each year.

Home Health Aides: Home health aides assist older adults and people with disabilities living at home with medical care. They may help with checking vital signs, assist with medical equipment, and help with administering medication. They may also help with activities of daily living (ADLs), which include eating, bathing, dressing, assisting with walking/exercise, and using the bathroom.

By Setting of Care:

Home Health: Home health agencies are organizations that provide skilled rehabilitative or post-acute care as well as long-term personal care for patients. The same skilled services provided by skilled nursing facilities, such as nursing, occupational therapy, and physical therapy, are instead provided in the home, along with assistance with ADLs and IADLs.

Services for the Elderly and People with Disabilities: These are services or settings that provide nonresidential, social assistance services for older adults and younger adults with disabilities. These establishments typically focus on the welfare of these individuals in such areas as day care, non-medical home care or homemaker services, social activities, group support, and companionship. These services and settings can include adult day care centers, home care services for older adults, and companion services.

Nursing Facilities: Nursing facilities are residential settings that provide round-the-clock nursing and personal care to residents who either need short-term rehabilitation following a hospitalization or injury or long-term care to residents with chronic medical and/or mental health conditions requiring access to 24-hour skilled care and assistance with ADLs or personal care.

Residential Care Facilities: These settings include residential settings that serve individuals with intellectual and developmental disabilitiesmental illness, or substance use disorder. These settings also include establishments that provide residential and personal care services for older adults or younger adults with disabilities who are unable to fully care for themselves. These settings can include assisted living facilitiescontinuing care retirement communities, and group homes for adults with disabilities. The care typically includes room, board, supervision, and assistance with activities of daily living.

Direct care workers are significantly more likely to be age 50 years or older, female, Black or Hispanic, or immigrants when compared to all other adult workers in the U.S. (Figure 2). Direct care workers are more likely to be age 50 years or older when compared to all other adult workers (41% vs 33%), as well as more likely to be female (85% vs 47%). They are also more likely to be Black than all other adult workers in the U.S. (30% vs 11%). They are also more likely to be Hispanic when compared to all other adult workers in the U.S. (23% vs 19%).Immigrants, including naturalized citizens and noncitizens, make up 30% of the overall direct care workforce, higher than the share of all adult workers in the U.S. who are immigrants (18%).

Direct care workers are also significantly more likely to have a high school degree or less, work part-time, be low-wage, and be covered by Medicaid or be uninsured when compared to all other adult workers in the U.S. (Figure 2). Direct care workers are more likely to have a high school degree or less than compared to all other adult workers (55% vs. 31%). They are also more likely to work part-time and make less than $35,000 annually (referred to as “low wage”) when compared to all other adult workers (39% vs 18%; 66% vs 31%). Direct care workers are also much more likely to be covered by Medicaid (32%) than all other adult workers (9%) and more likely to be uninsured when compared to all other adult workers (13% vs. 9%).
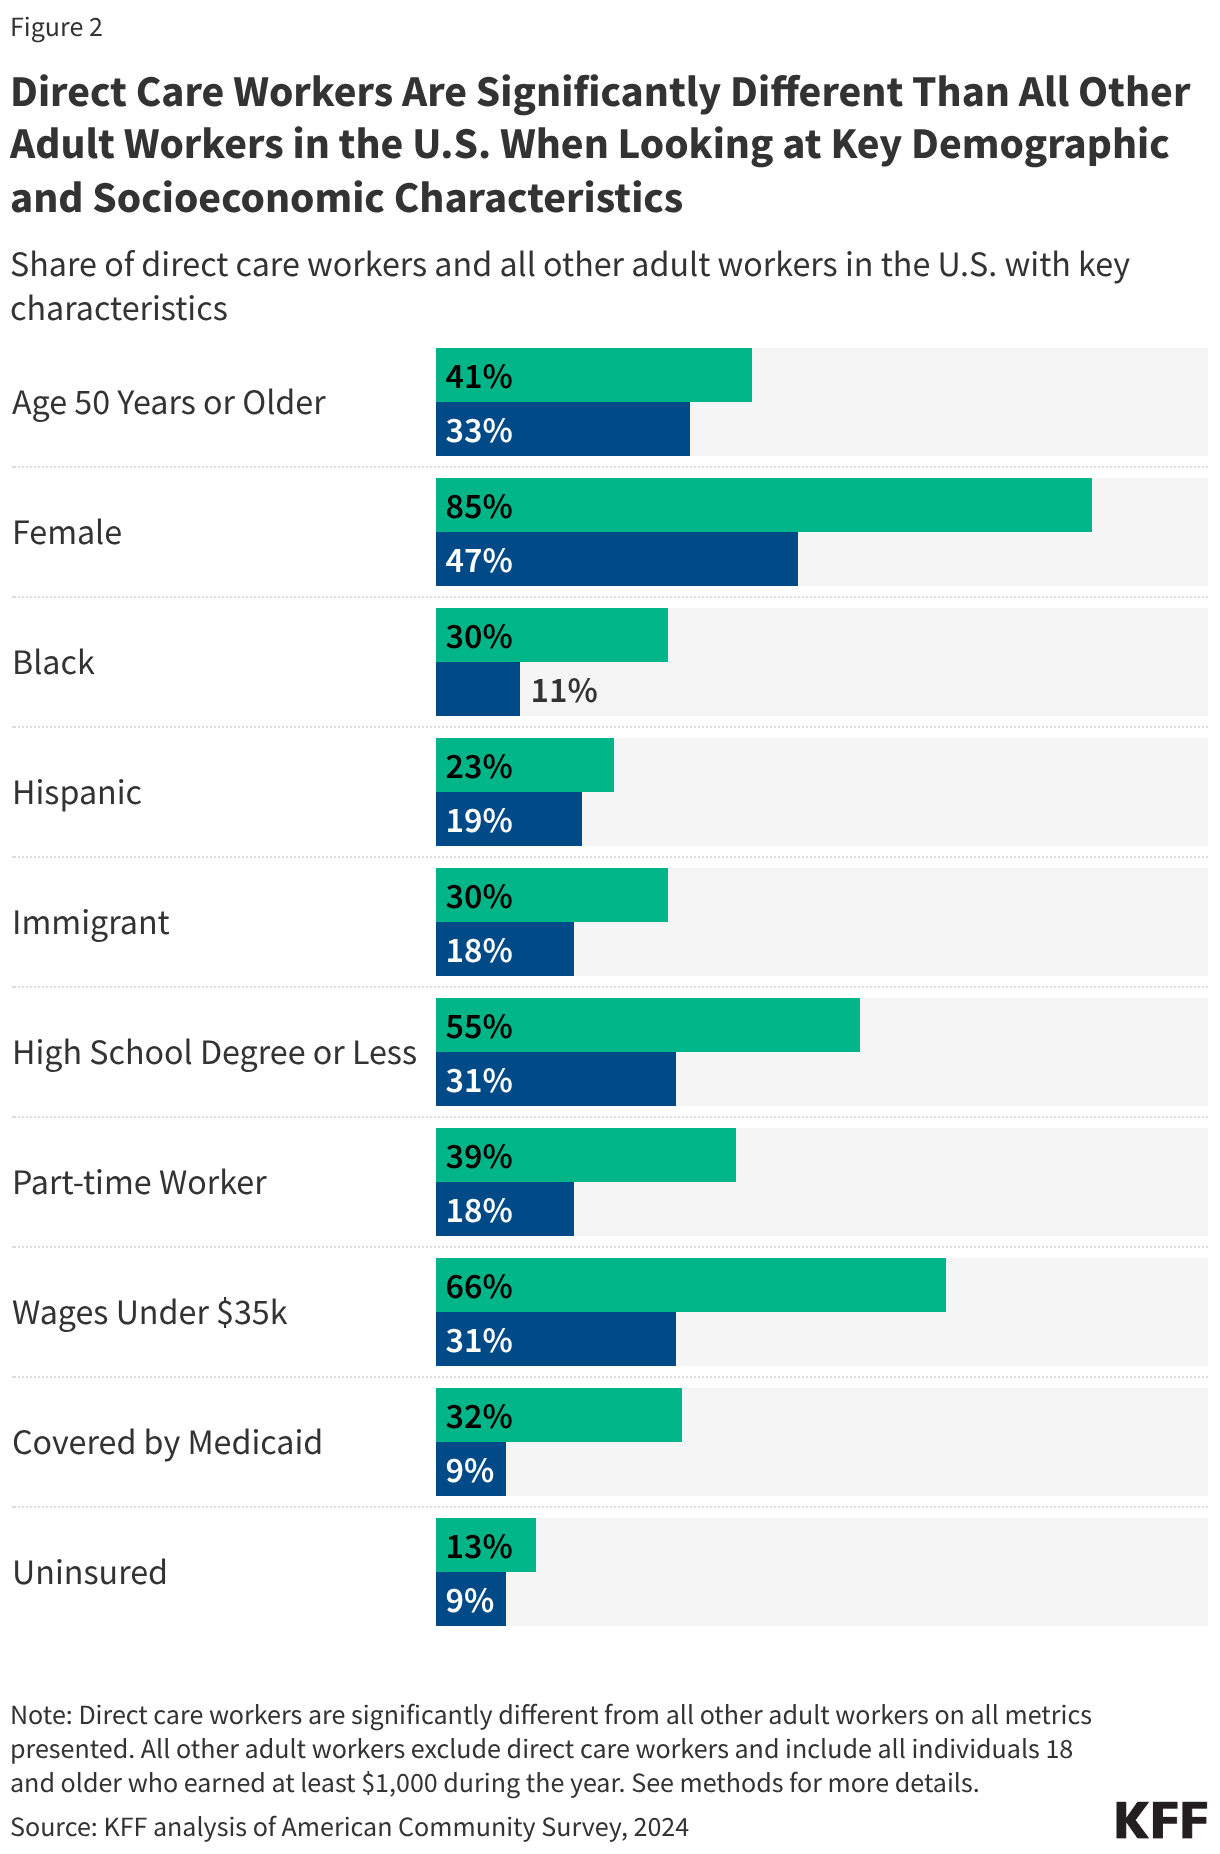
Direct Care Workers Are Significantly Different Than All Other Adult Workers in the U.S. When Looking at Key Demographic and Socioeconomic Characteristics (Grouped Bars)

Direct care workers in home care settings are different than direct care workers in nursing homes or residential care facilities (Appendix Table 1). A higher share of direct care workers in home care settings are immigrants (33%) when compared to direct care workers in nursing facilities (25%) and residential care facilities (23%) (Figure 3). Additionally, a higher share of direct care workers in home care settings work part-time (42%) when compared to workers in nursing homes (24%) and residential care facilities (25%). Similarly, a higher share of home care workers are low-wage (72%) when compared to those working in nursing homes (56%) or residential care facilities (58%) (Appendix Table 1).

Immigrants make up 30% of the overall direct care workforce providing long-term care services (Figure 3). Naturalized citizens make up a significantly larger share of direct care workers in home care settings (19%) when compared to nursing facilities (16%) and residential care settings (14%). Home care workers are also significantly more likely to be noncitizen immigrants (14%) when compared to workers in nursing homes (9%) and residential care facilities (9%). Noncitizen immigrants include both lawfully present and undocumented immigrants.
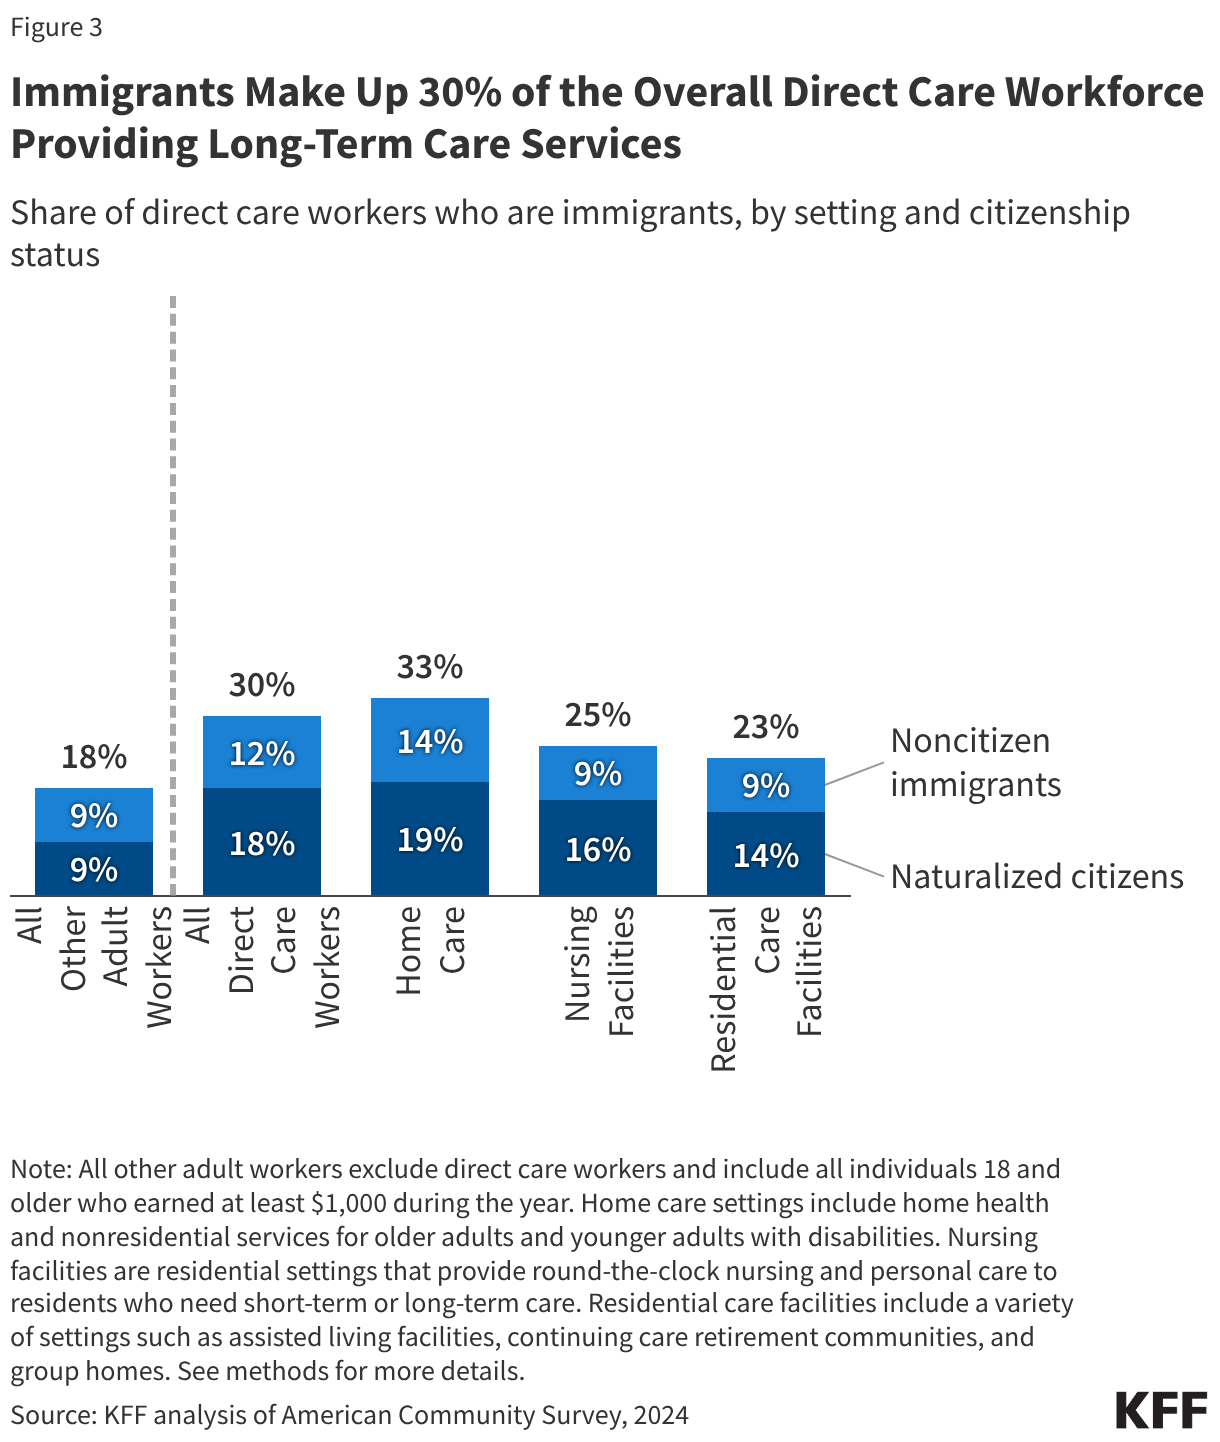
Immigrants Make Up 30% of the Overall Direct Care Workforce Providing Long-Term Care Services (Stacked column chart)

The share of direct care workers who are immigrants varies by state, ranging from 0% in Wyoming to 60% in New York, and, in many cases, reflects the share of overall immigrant workers (Figure 4). In 20 states, including many Southern states, the share of direct care workers who are immigrants is under 10%. In 9 states, the share of direct care workers who are immigrants is between 10% and 19%. In 9 states, 20% to 29% of direct care workers are immigrants, and in the remaining 13 states (including DC), 30% or more of direct care workers are immigrants. The share of direct care workers who are immigrants is strongly positively correlated with the overall share of workers in a state that are immigrants.
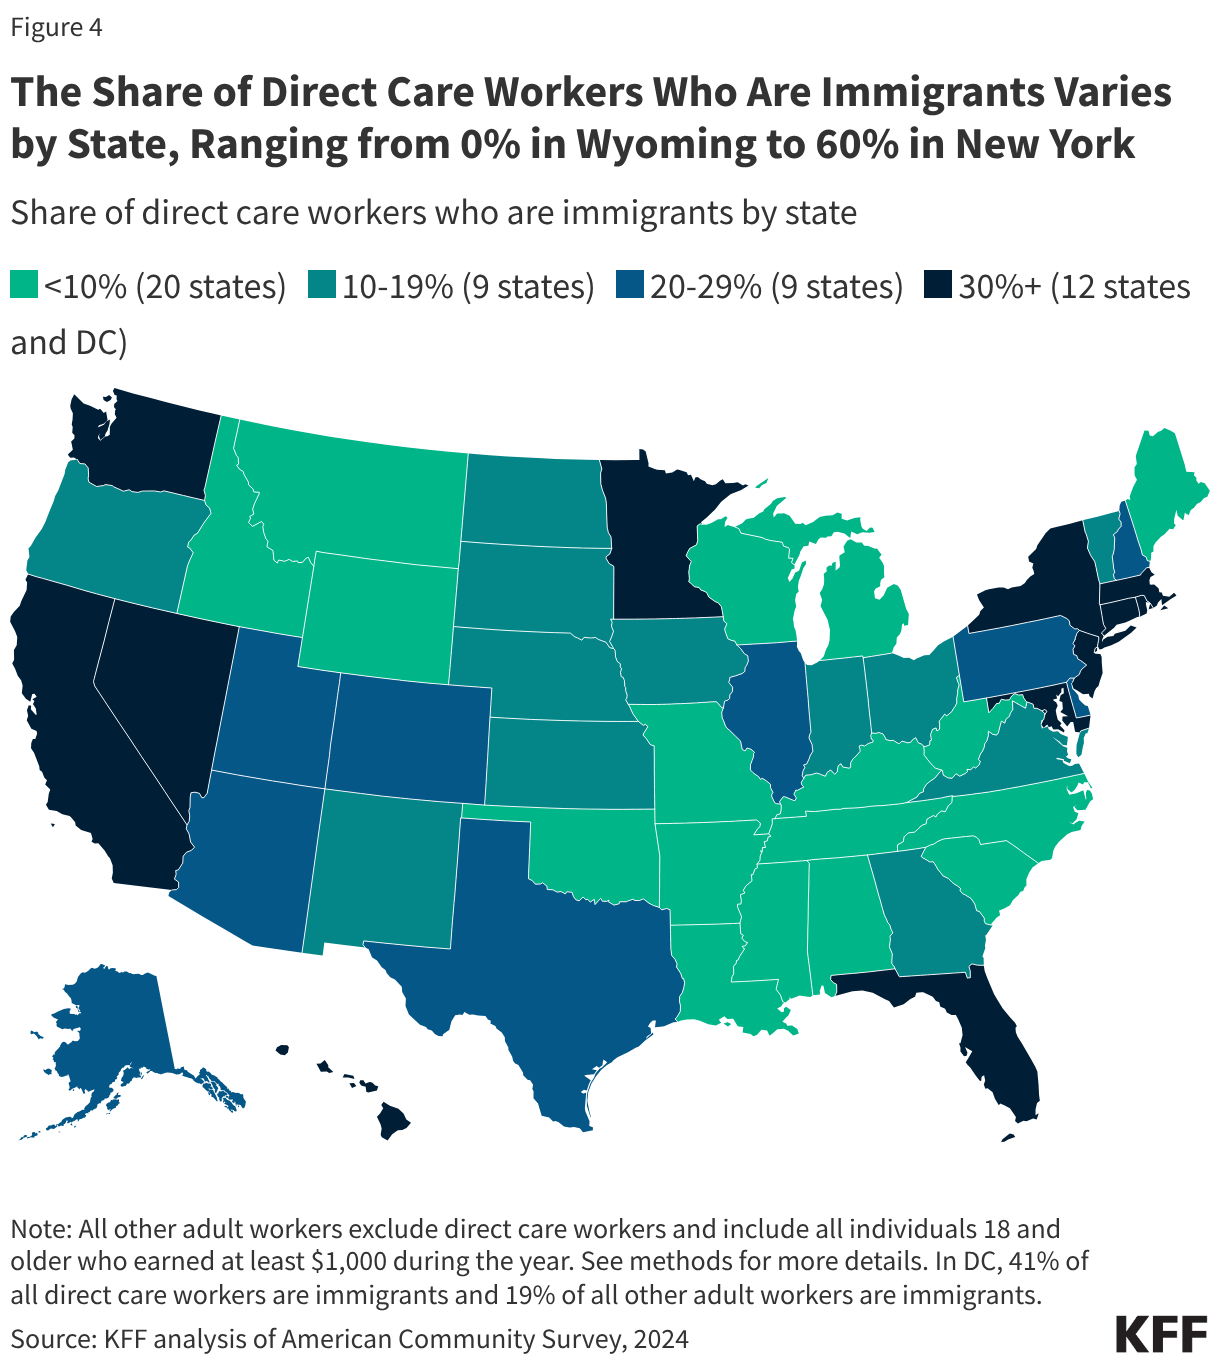
The Share of Direct Care Workers Who Are Immigrants Varies by State, Ranging from 0% in Wyoming to 60% in New York (Choropleth map)

Immigrants from 13 countries make up nearly two-thirds (65%) of all immigrant direct care workers providing long-term care in the U.S. (Figure 5). The remaining one-third of immigrant direct care workers come primarily from a mix of countries in South and Central America, Africa, and Asia. Six countries each account for 5% or more of immigrant direct care workers: Mexico (14%), Dominican Republic (7%), Philippines (7%), Jamaica (6%), China (6%), and Haiti (6%).

At least one in five immigrant direct care workers is from a country that is part of the Trump administration’s immigrant visa pause (Figure 5). Among the top 13 countries that make up nearly two-thirds of immigrant direct care workers, five of them are part of the Trump administration’s immigrant visa pause (Jamaica, Haiti, Nigeria, Cuba, and Ghana) that impacts 75 countries. While the immigrant visa pause is facing a court challenge, it currently remains in effect. On June 25, 2026, the Supreme Court issued a ruling allowing the Trump administration to proceed with terminating Haiti’s TPS designation, which could impact over 300,000 Haitian TPS holders. These policies could further strain the workforce in future years.
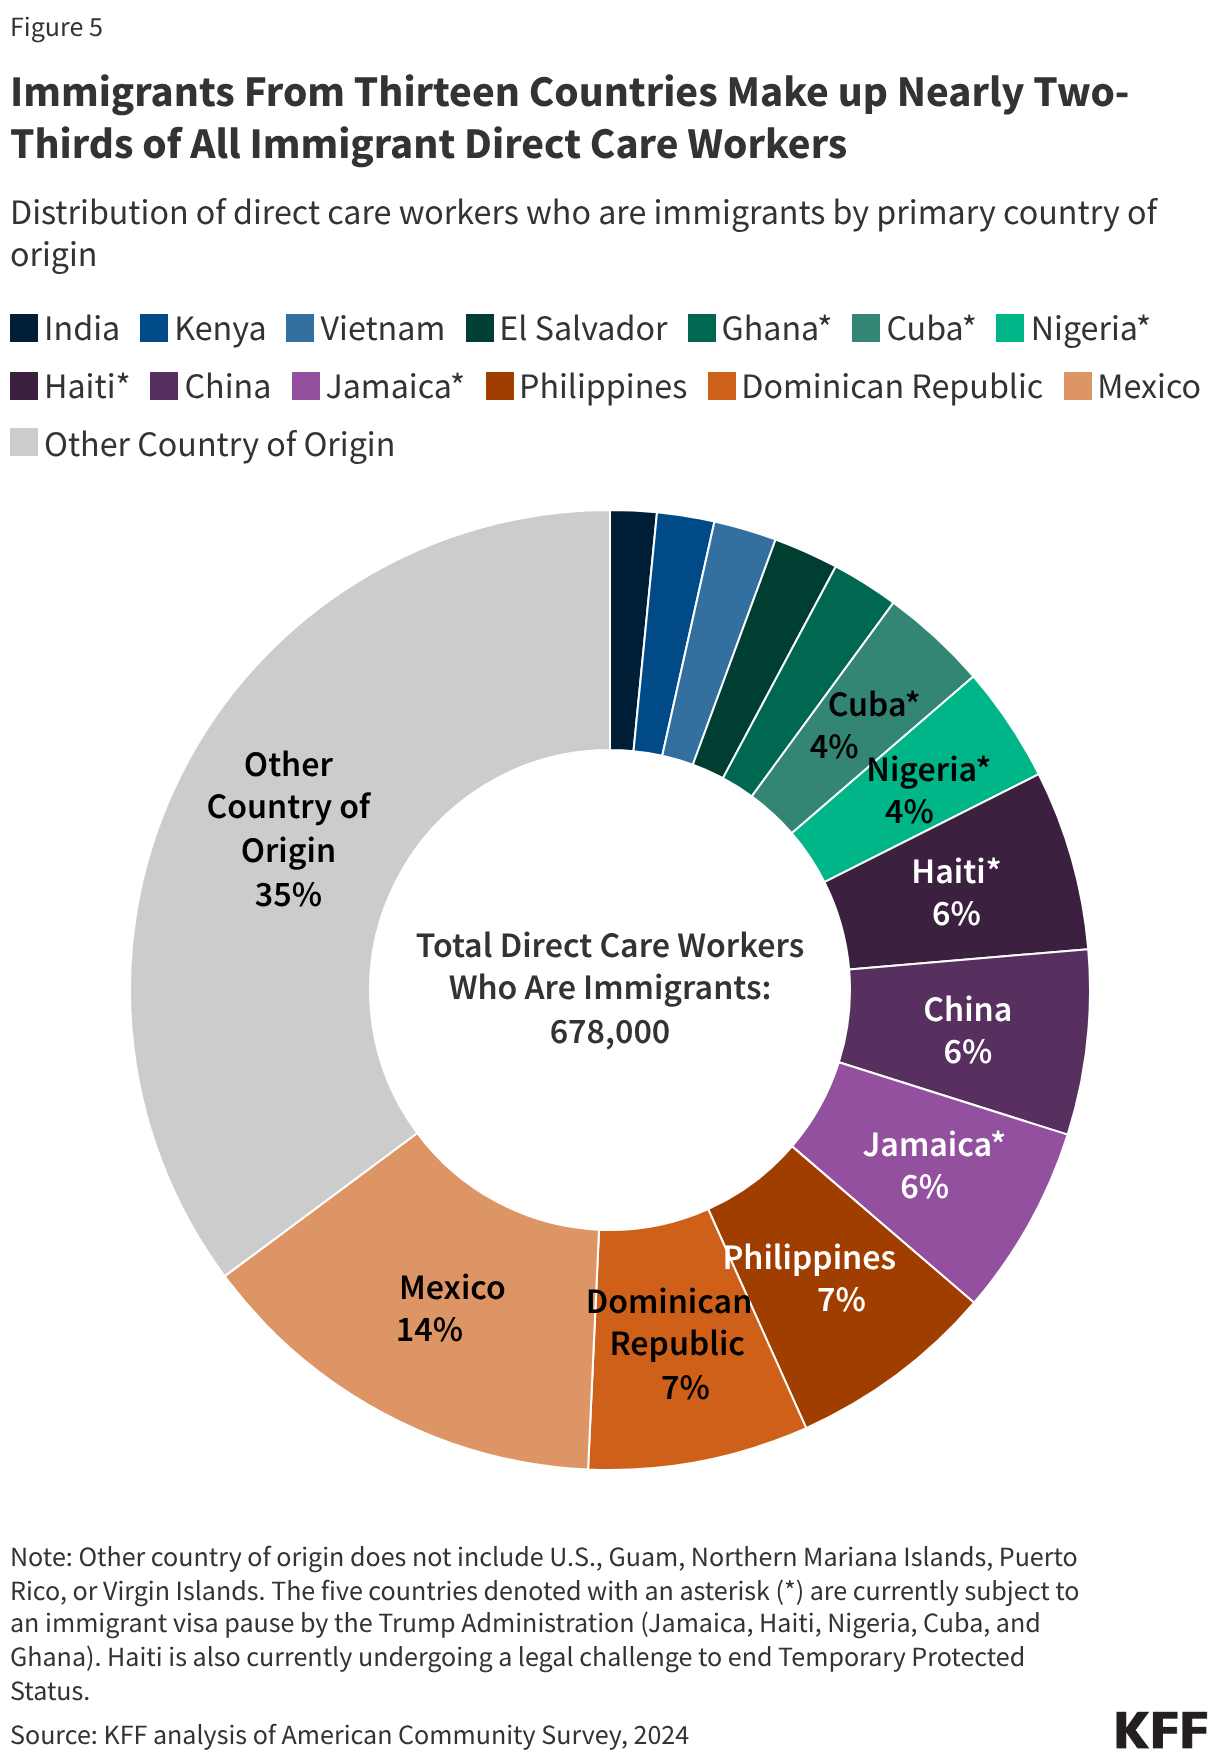
Immigrants From Thirteen Countries Make up Nearly Two-Thirds of All Immigrant Direct Care Workers (Donut Chart)

Methods

Data: These findings are based on KFF analysis of the 2024 American Community Survey (ACS) 1-year Public Use Microdata Sample (PUMS) files. The ACS includes a 1% sample of the U.S. population, and the subset of direct care workers used here includes 19,612 observations.

Identifying Direct Care Workers in ACS: Direct care workers are those who fall into the following occupation codes: Home health aides (3601); Personal care aides (3602); and Nursing assistants (3603). This analysis only includes those who work in the following industries: Home Health Care (8170), Nursing Care Facilities (8270), Residential Care Facilities (8290), and Individual and Family Services (8370). “Individual and family services” are also referred to as “services for the elderly and people with disabilities.” Home health care and individual and family services are collapsed into “Home care” for this analysis. These industries capture most workers providing long-term health services. The ACS only includes the primary industry and occupation of a respondent’s current or most recent (in case the respondent is not currently working) job.

We define the direct care workforce as all individuals 18 and older who earned at least $1,000 during the year and indicated that their job was in both the long-term care industry and occupation codes listed above. The comparison group “All Adult Workers in the U.S.” includes all individuals 18 and older who earned at least $1000 during the year.

Health Insurance Coverage in ACS: The ACS asks respondents about their health insurance coverage at the time of the survey. Respondents may report having more than one type of coverage; however, individuals are sorted into only one category of insurance coverage. See notes here for more information on the insurance coverage hierarchy.

Identifying Immigrants in ACS: Immigrants are identified as those who report their citizenship status (variable name: CIT) in ACS as being a “U.S. citizen by naturalization” or as “not a citizen of the U.S.”, with the former being grouped under “naturalized citizens” and the latter being grouped under “noncitizen immigrants” for the purpose of this analysis. Noncitizen immigrants include lawfully present and undocumented immigrants.

Appendix
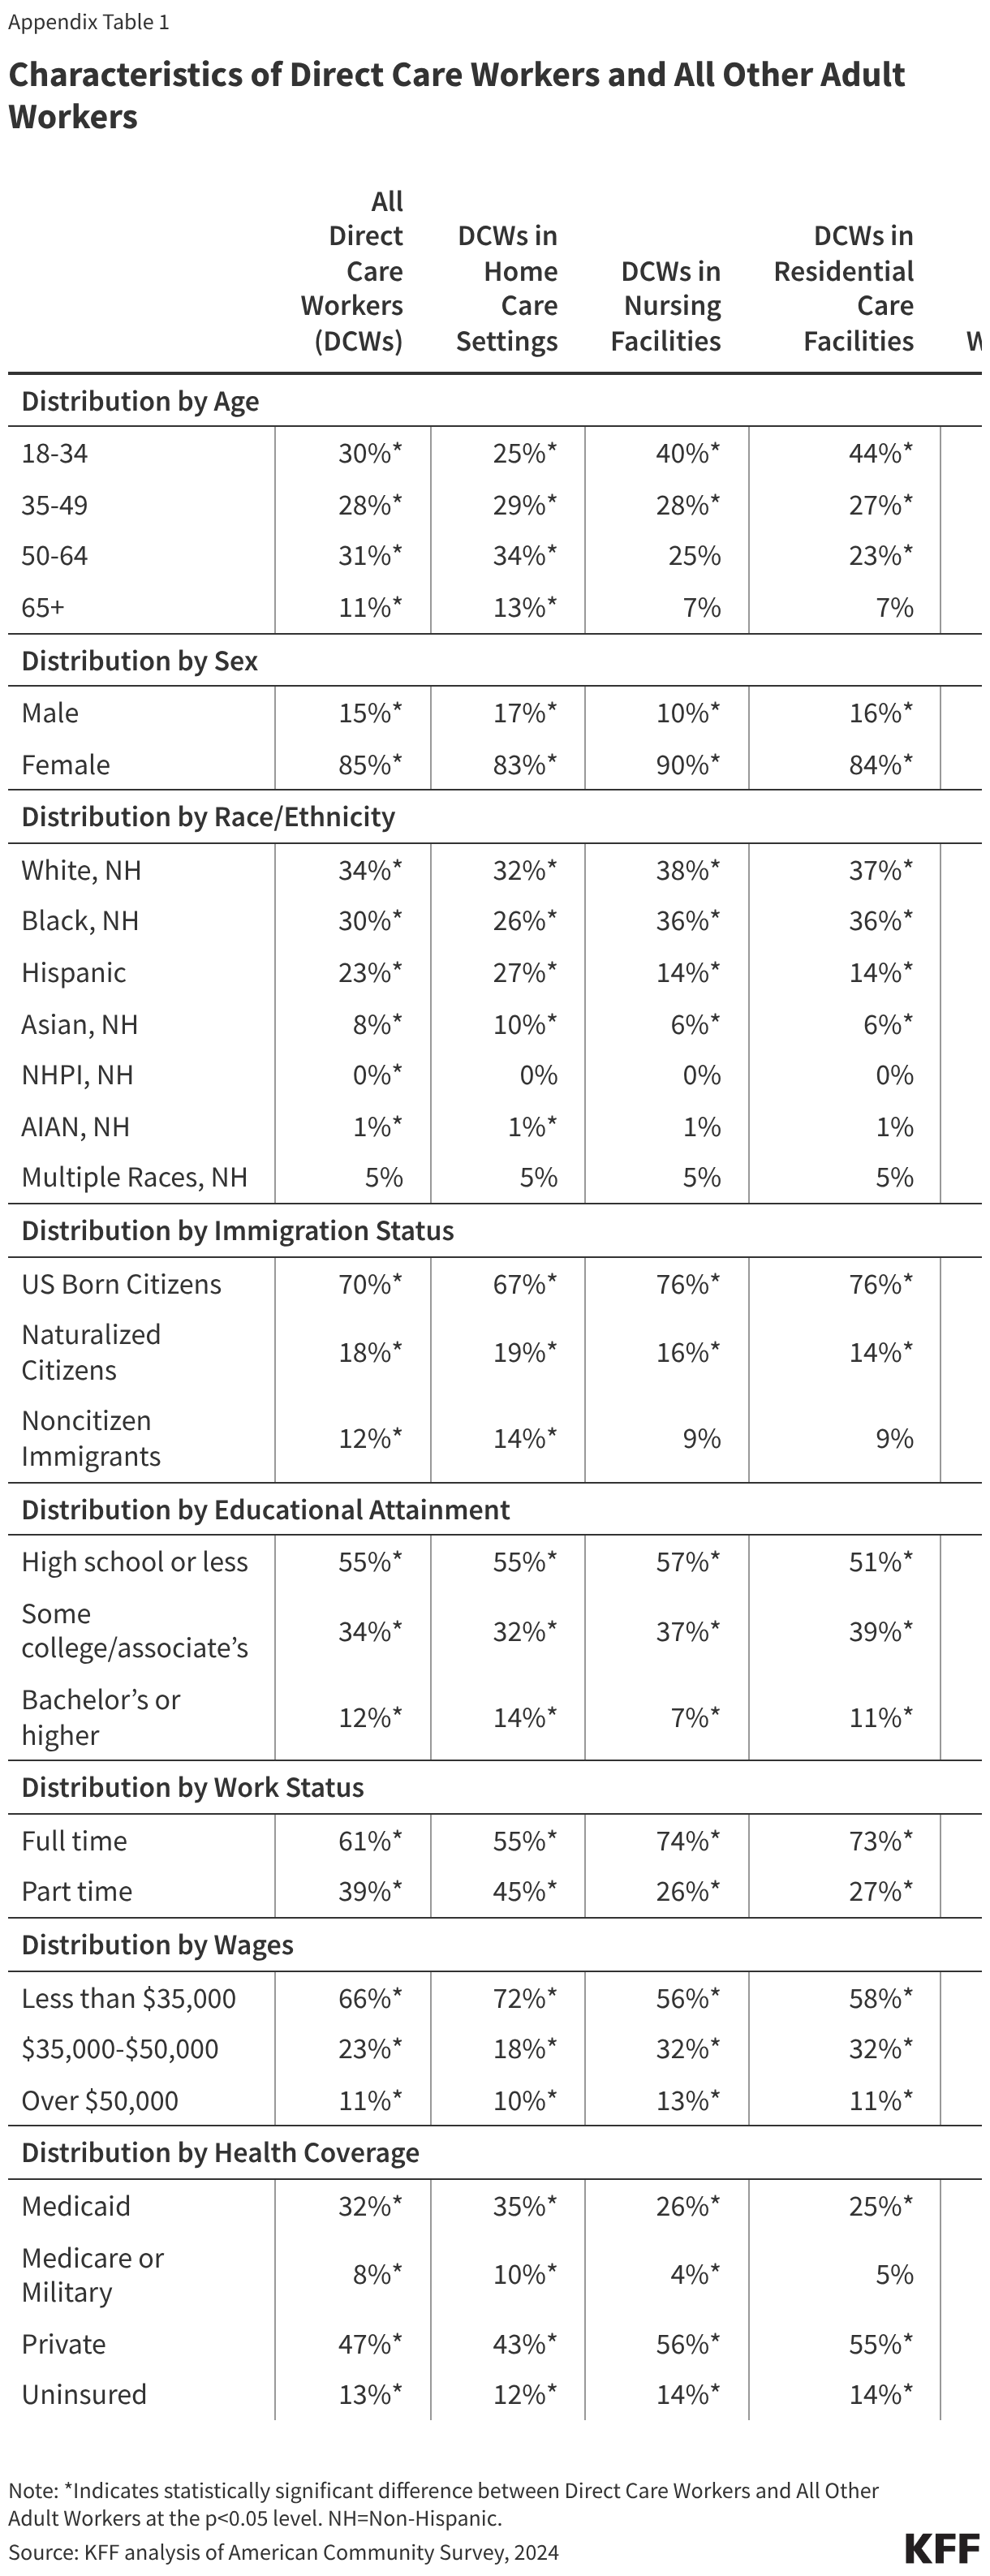
Characteristics of Direct Care Workers and All Other Adult Workers (Table)

VOLUME 50

New KFF Poll Examines Patterns of Belief Across Common Vaccine Myths


Highlights

KFF’s latest Tracking Poll on Health Information and Trust shows that larger shares of the public express uncertainty over common vaccine myths than definitive belief. The latest analysis, looking at patterns of belief across vaccine myths, shows which adults are consistent myth believers, consistent myth deniers, and those who fall in the “mixed middle” whose views are less defined and may be an important focus for those looking to counter vaccine misinformation. These findings, including a detailed explainer on patterns of belief across vaccine myths, can also be found on KFF’s interactive Health Information and Trust Polling Dashboard.


Americans May Be Smarter About Vaccines Than You Think

In a “Beyond the Data” column exploring KFF’s latest Tracking Poll on Health Information and Trust, KFF’s Founding President and CEO Drew Altman writes that Americans who firmly believe vaccine myths are vastly outnumbered both by those who believe science and those who remain uncertain. He suggests that amplifiers, including influencers, officials, and the media, may spread confusion and uncertainty about health claims.

KFF Poll Looks at Patterns of Belief Across Myths, Finding That Three in Ten Fall in the “Mixed Middle,” A Group That May Be an Important Focus for Dispelling Myths

The latest KFF Tracking Poll on Health Information and Trust examines the pervasiveness of and belief in several common vaccine myths, including that the MMR vaccines have been proven to cause autism; that measles vaccines are more dangerous than measles; that more people died from COVID-19 vaccines than from the virus; and that mRNA vaccines can change your DNA. 

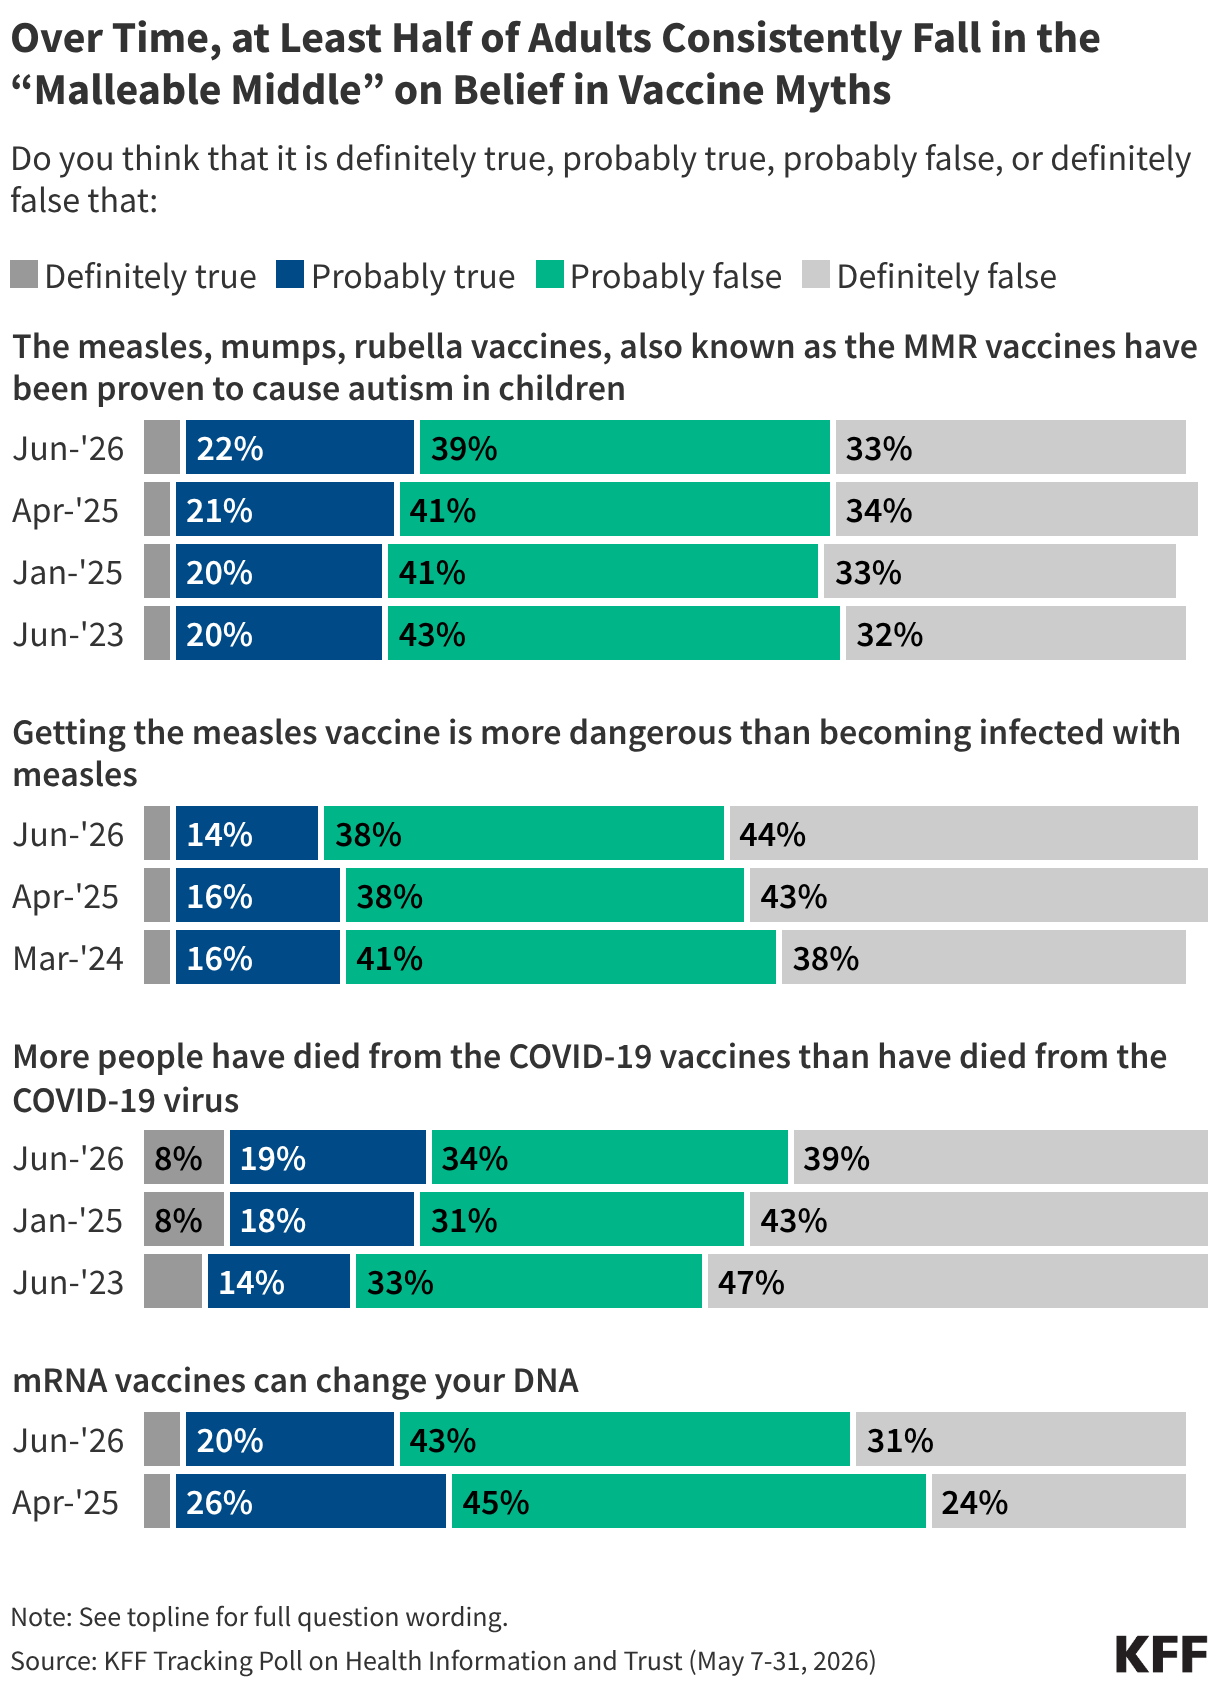
Over the past several years, fewer than one in ten adults have said each of these myths are “definitely true,” while much larger shares (but fewer than half of adults) say they are “definitely false.” At the same time, at least half consistently fall in the “malleable middle,” expressing some uncertainty and saying the myths are either “probably true” or “probably false.” This dynamic has remained relatively stable over several years of KFF polling, though there have been some minor shifts in the share who say some of these myths are “definitely false,” reflecting how beliefs are not often completely fixed.

Stacked bar chart showing how belief in four false vaccine claims has changed over time, from June 2023 to June 2026.

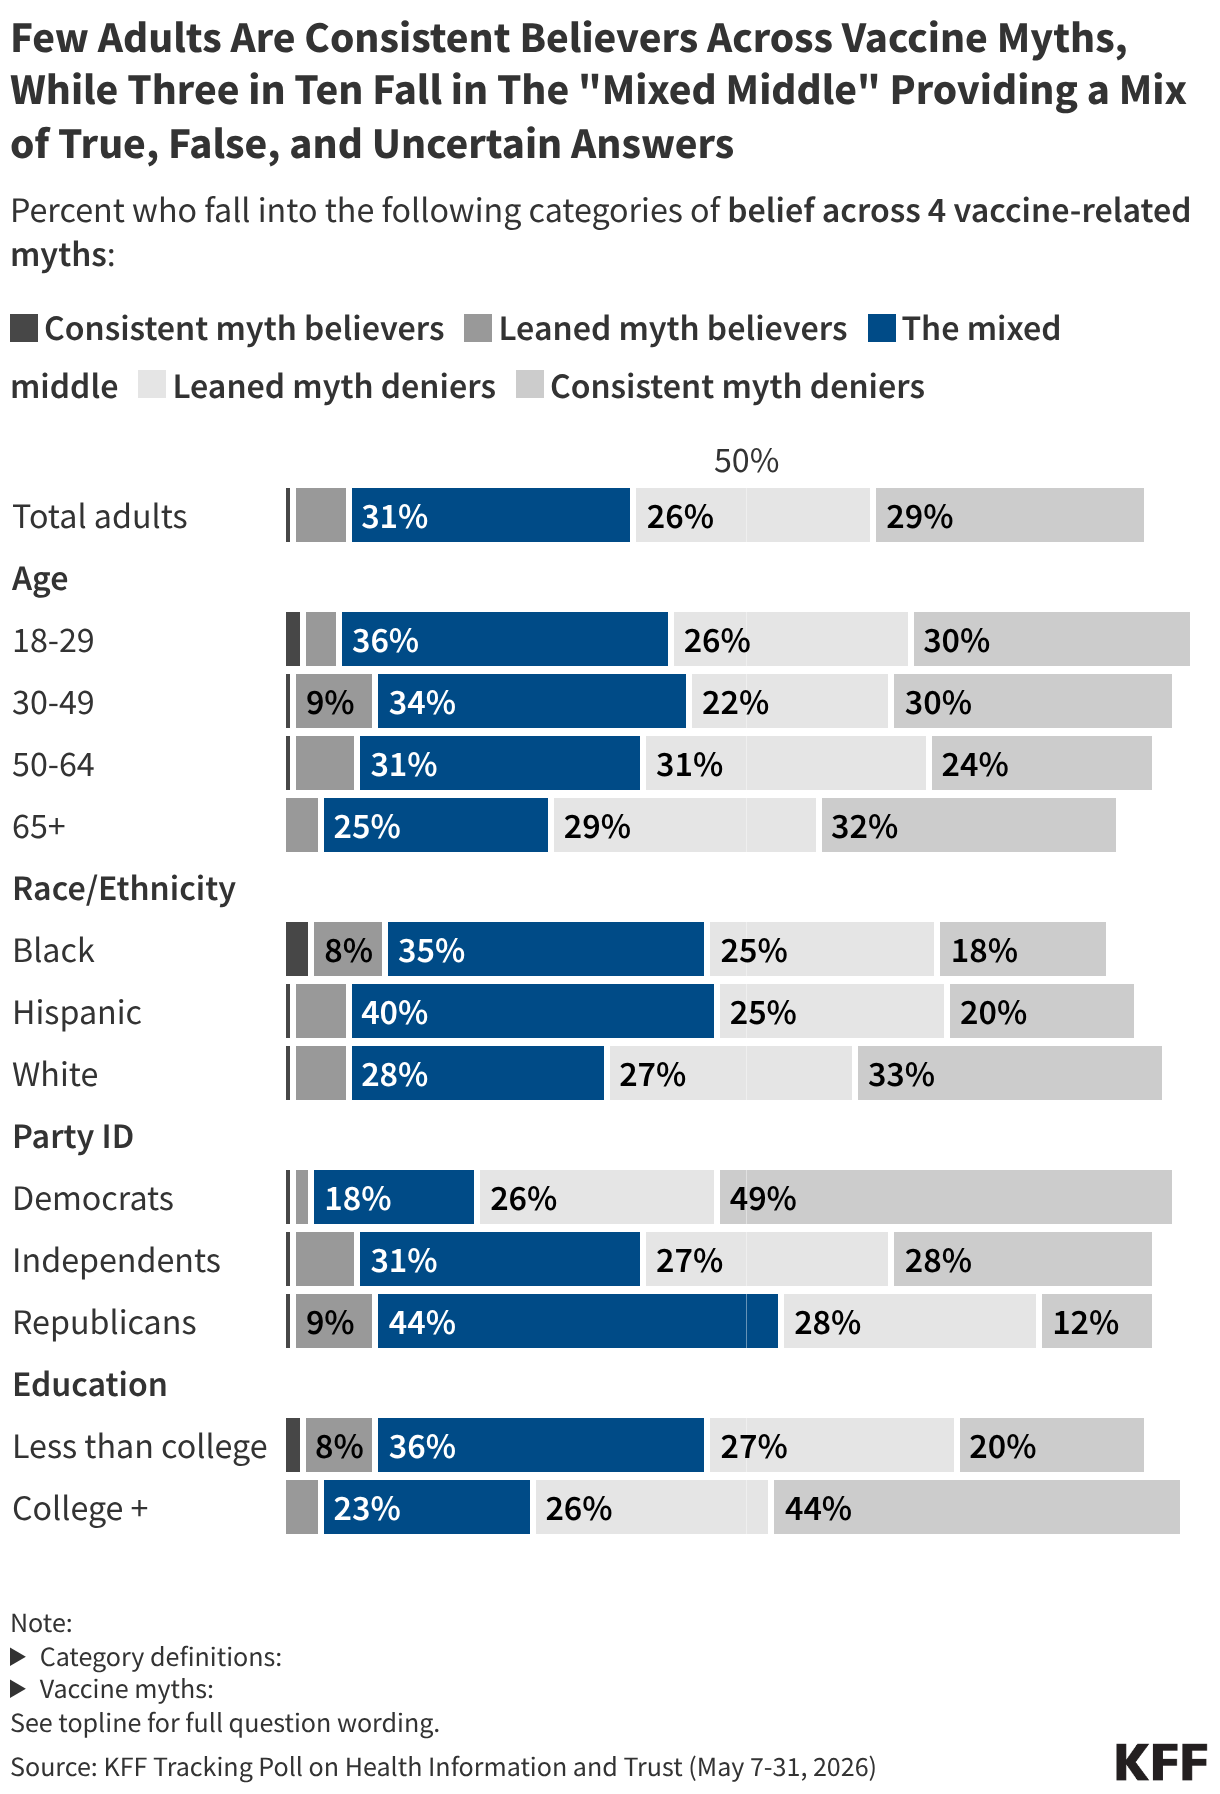
KFF’s latest poll also includes a new analysis looking at a typology of belief across these four vaccine myths. While at least half the public express some uncertainty over individual false vaccine claims, there are nuances to this group that can be examined by looking at patterns of belief across myths. Relatively few adults are consistent myth believers (1%) who say all four are true, including at least three that are “definitely true,” or leaned myth believers (6%) who say all the myths are true, but express more uncertainty saying at least half are “probably true.” Larger shares are on the side of the truth, including consistent myth deniers (29%) who say all four myths are false, including at least three as “definitely false,” and leaned myth deniers (26%), who say all are false, but at least half as “probably false.” Another three in ten adults (31%) fall in the mixed middle, a group that includes those who provide a range of true and false responses and lack certainty across at least half of the vaccine myths, saying they are either “probably true” or “probably false.”

This analysis provides a new lens for understanding different segments of the public who may benefit from different public health communications strategies. For example, adults in the “mixed middle” represent a share of the public who more routinely express doubt and do not consistently lean toward believing or denying vaccine myths. Given their higher levels of uncertainty, this “mixed middle” may be a key group to focus on for those who are looking to counter false information about vaccines. Larger shares of younger adults, Black adults, Hispanic adults, Republicans, and those without a college education fall into this “mixed middle” group.

Health information sources are also tied to uncertainty across vaccine myths: those who weekly use social media or artificial intelligence (AI) chatbots for health information are more likely to fall in the “mixed middle” than those who never use these platforms.

Stacked bar chart showing the percentage of adults who fall into five belief categories — consistent myth believers, leaned myth believers, the mixed middle, leaned myth deniers, and consistent myth deniers — across four vaccine-related myths, broken down by total adults, total parents, age, race and ethnicity, party identification, and education.

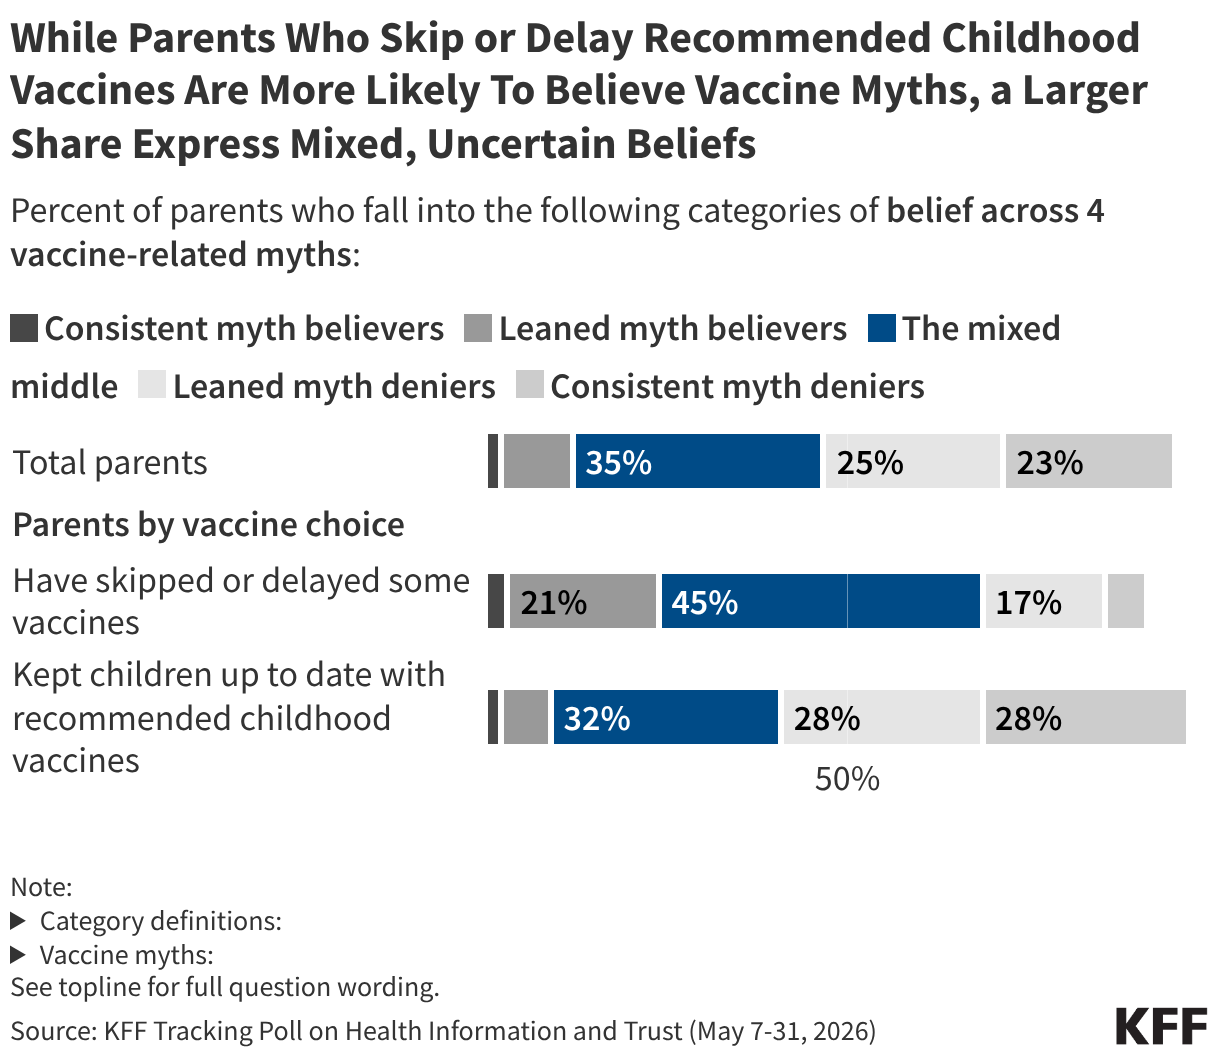
Notably, while parents who report skipping or delaying recommended vaccines are much more likely than those who keep their children up to date to believe or lean toward believing vaccine myths, nearly half of parents who report skipping or delaying some childhood vaccines fall in the “mixed middle.” This analysis shows that parents who are skipping or delaying vaccines for their children are more likely to express confusion and inconsistent beliefs across vaccine myths rather than consistent beliefs, which may reflect the potential for interventions to deliver accurate information among this group.

Stacked bar chart showing the percentage of parents who fall into five belief categories — consistent myth believers, leaned myth believers, the mixed middle, leaned myth deniers, and consistent myth deniers — across four vaccine-related myths, broken down by total parents and by whether they have skipped or delayed their children's vaccines or kept them up to date.

What We’re Watching

FDA Advisory Panel Recommends First mRNA Flu Vaccine, though Public Uncertainty About the Technology Persists

A Food and Drug Administration (FDA) advisory committee voted unanimously last month to recommend Moderna’s mRNA-based influenza vaccine for adults 50 and older. The committee’s recommendation is not a final approval, but if the vaccine is approved by the FDA, it would become the first flu vaccine in the U.S. to use the same mRNA technology deployed in COVID-19 vaccines. Moderna and panel members explained that using mRNA would enable vaccines to be produced and updated more quickly as strains change.

The vote has drawn renewed attention to mRNA vaccines online, with some online conversations misrepresenting both the technology’s safety and the scope of the vote. One physician with more than 600,000 followers suggested that all flu vaccines would use mRNA technology in the next flu season and urged followers to avoid them. Another post, from an attorney and podcast host, characterized the vote as part of a bigger plan to replace all vaccines with mRNA technology. Others revived false claims about mRNA vaccines from the COVID-19 pandemic, including that they can alter a person’s DNA or cause widespread health harms.

In reality, the committee’s recommendation applies only to one mRNA-based flu vaccine for adults 50 and older and would not affect traditional flu vaccines for most people. More than 6 billion doses of mRNA vaccines have been administered globally since 2020, and there is no evidence the technology alters human DNA or poses widespread health risks.

Why This Matters: KFF polling finds that roughly a third of adults (36%) have heard the claim that mRNA vaccines can alter a person’s DNA, and most people are uncertain whether it’s true or false. Exposure to this claim has declined 9 percentage points since April 2025, and the share who say the claim is “definitely false” has increased moderately over the same period. Past KFF polling also found that mRNA technology was obscure to much of the public, with about half (52%) reporting they didn’t know enough about it to say whether it was safe, larger than the shares who viewed it as either generally safe (32%) or generally unsafe (16%). As a new mRNA-based vaccine moves through the regulatory process, false narratives may find a receptive audience among adults who remain uncertain about the technology’s safety. The mRNA vaccine would be an additional option rather than a replacement for existing vaccines, but KFF will monitor whether uncertainty about the scope of the recommendation and mRNA’s safety could lead some to decline flu vaccination altogether.

Delayed Publication of Federal COVID Vaccine Study Highlights Disputes Over Agencies’ Scientific Independence

A study led by the Centers for Disease Control and Prevention (CDC) estimating COVID-19 vaccine effectiveness was published last week in a medical journal, months after acting CDC Director Jay Bhattacharya canceled its publication in the agency’s own weekly scientific report, citing methodological concerns. The study, which had been slated for publication in March in the CDC’s Morbidity and Mortality Weekly Report (MMWR), estimated the 2025-26 COVID-19 vaccine reduced COVID-associated emergency department visits and hospitalizations by at least 50%.

The study’s underlying approach, known as test-negative design, compares vaccination status among patients who test positive for a virus against those who test negative for the same symptoms. Bhattacharya has said he favors longitudinal cohort studies and raised concerns that test-negative studies may not adequately account for factors like prior infection.

A commentary published alongside the study, though, defended test-negative design as a long-standing, widely used approach for monitoring vaccine effectiveness. The CDC has long used this methodology to monitor flu vaccines, with a report about last winter’s flu vaccine effectiveness published in MMWR just a week before the COVID study was originally scheduled for publication. A co-author of the COVID study characterized the decision to withhold it from MMWR as “clearly not for scientific reasons” and said she believed it instead reflected the administration’s general stance on COVID-19 vaccines. HHS disputed that characterization, saying the agency does not make decisions based on predetermined conclusions.

Why This Matters: KFF polling has found that fewer than four in ten adults (38%) are confident that federal health agencies make decisions based on science rather than the personal views of agency officials, and fewer than half express confidence in agencies such as the CDC (40%) or FDA (36%) to act independently, without interference from outside interests. Disputes like this one, over a long-used and widely accepted research method, may also create confusion, potentially undermining confidence in the surveillance tools used to monitor vaccines.


AI & Emerging Technology

AI Chatbots Matched, But Didn’t Outperform, Existing Public Health Materials in Encouraging HPV Vaccination

A study published last month in JAMA Network Open found that brief conversations with an AI chatbot were no more effective than pre-existing public health materials at increasing parents’ intent to vaccinate their children against human papillomavirus (HPV), and the chatbot’s effects faded faster. Among more than 1,200 parents, researchers compared pre-existing public health materials from federal agencies like the CDC against a chatbot built using a standard AI model and instructed to respond to each parent’s top reason for not vaccinating. Both increased parents’ stated intent to vaccinate immediately afterward, but by 45 days, only the written materials maintained that effect. Neither approach meaningfully increased vaccination rates.

KFF and the Washington Post’s Survey of Parents showed that about one in five parents of children too young for HPV vaccination say they would “probably not” or “definitely not” vaccinate their child against the virus. Research conducted before the COVID-19 pandemic found that parents’ top reasons for not vaccinating their children against HPV were safety concerns and the belief that the vaccine wasn’t needed. 

Why This Matters: As funding for traditional vaccination outreach becomes more scarce, some health departments may be looking for lower-cost alternatives to existing public health materials. This study suggests, however, that AI may not be an effective replacement for those existing tools. The study’s other finding, that even communications that impacted intentions didn’t result in more children getting vaccinated, demonstrates that changing intent doesn’t reliably change behavior, with researchers theorizing that practical barriers like scheduling a pediatrician visit may stand between intention and action.

About The Health Information and Trust Initiative: the Health Information and Trust Initiative is a KFF program aimed at tracking health misinformation in the U.S., analyzing its impact on the American people, and mobilizing media to address the problem. Our goal is to be of service to everyone working on health misinformation, strengthen efforts to counter misinformation, and build trust. 


View all KFF Monitors

The Monitor is a report from KFF’s Health Information and Trust initiative that focuses on recent developments in health information. It’s free and published twice a month.

Sign up to receive KFF Monitor
email updates


Support for the Health Information and Trust initiative is provided by the Robert Wood Johnson Foundation (RWJF). The views expressed do not necessarily reflect the views of RWJF and KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities. The data shared in the Monitor is sourced through media monitoring research conducted by KFF.

How Unaffordable is Health Care? 

A Video Series from KFF

Published: Jul 9, 2026

Heading into the 2026 midterms, KFF’s survey research shows that health care affordability is a top issue for voters. Why and how did care get so expensive?  

This three-part video series from KFF helps people understand the rising cost of health care in the U.S., from the macro level to the issues facing everyday Americans.

Drawing on KFF policy analysis and polling and narrated by KFF experts, the videos look at the underlying drivers of health care spending, the true cost of employer sponsored health insurance and whether the Affordable Care Act has delivered on its promise.


Watch and share the full series. Available on YouTube. 

KFF encourages linking to and reposting of our content on social media and other digital platforms.

Choose a video from our YouTube channel, click the Share button, select Embed, and copy the generated <iframe> code. Paste this HTML code directly into your websites editor or source code.

For collaboration or to request direct video downloads (vertical and horizontal formats) and carousel graphics, email us at outreach@kff.org

Subscribe to the KFF YouTube Channel. Stay connected with KFF on other social platforms

When citing us, please note our legal name is KFF. We should be cited as KFF, a nonprofit health policy research, polling, and news organization. Our name is no longer the Kaiser Family Foundation. More about KFF citations and permissions. 

The videos were scripted and produced by KFF. Visuals and graphics were developed using Adobe Creative Cloud with assistance from AI tools and refined by a graphic designer. Additional content: C-SPAN.

Total Run Time: 2:02

Total Run Time: 1:58

Health Care Costs Keep Rising … Why and Who Pays?

Narrated by:

Published:

The U.S. spends more on health care than other large, wealthy countries. Concerns about rising costs aren’t new, yet somehow we keep paying the bill. 

KFF’s Larry Levitt, Executive Vice President for Health Policy, explains how we got here, who bears the consequences and why reining in spending systematically may be central to the next big health care debate.


Watch and share the full series. Available on YouTube. 

KFF encourages linking to and reposting of our content on social media and other digital platforms.

Choose a video from our YouTube channel, click the Share button, select Embed, and copy the generated <iframe> code. Paste this HTML code directly into your websites editor or source code.

For collaboration or to request direct video downloads (vertical and horizontal formats) and carousel graphics, email us at outreach@kff.org

Subscribe to the KFF YouTube Channel. Stay connected with KFF on other social platforms

When citing us, please note our legal name is KFF. We should be cited as KFF, a nonprofit health policy research, polling, and news organization. Our name is no longer the Kaiser Family Foundation. More about KFF citations and permissions. 

The videos were scripted and produced by KFF. Visuals and graphics were developed using Adobe Creative Cloud with assistance from AI tools and refined by a graphic designer. Additional content: C-SPAN.


Video Transcript

Narrated by Larry Levitt, KFF Executive Vice President for Health Policy

It’s hardly controversial to assert that U.S. health care is far less affordable compared with the rest of the world. 

In 2024, the U.S. spent $14,775 per person on health care compared to $7,860 per person in other high-income countries. 

That’s 88% higher than other large, wealthy countries.

Concerns about rising health care costs aren’t new. 

President Barack Obama said in 2009 that the soaring costs of health care make our current course unsustainable. 

President Bill Clinton said in 1992 that health care costs were increasing at unsustainable rates. 

In 1971, President Richard Nixon described a growing crisis in health care, when national health spending had reached what was then an unthinkable 7% of the economy. 

By 2024, U.S. healthcare spending had reached 18% of GDP. 

Somehow, we keep paying the bill even as health spending continues to increase. But there are consequences to rising health care costs. Health spending crowds out other spending priorities for federal, state, and local governments. 

For employers, the rising cost of health benefits can reduce profits, hurt international competitiveness, increase prices, and result in stagnating wages for workers. 

For individuals, unaffordable health care costs can create barriers to care and result in crushing medical debt, bankruptcy, falling behind on other household expenses, and poorer health. 

While government subsidies and employer contributions to health benefits can reduce out-of-pocket premiums for individuals, those costs must be borne by someone. 

And as health care costs increase, there is pressure on the government to reduce spending on health programs and on employers to shift costs to workers. 

Ultimately, the only way to achieve greater health care affordability systematically is to lower underlying health care costs, especially the price of care for hospitals and prescription drugs. 

And that may be central to the next big health care reform debate.

MORE HEALTH POLICY VIDEOS

KFF video series titled "Are Health Insurers the Problem?" features a man in a suit shrugging with a confused expression, surrounded by illustrated symbols of loudspeakers, exclamation marks, and lightning bolts, suggesting debate or controversy. The YouTube logo is shown at the bottom left.

Series

Health in the 2026 Midterm Elections

This research is part of KFF’s Health in the Midterms series, a collection of policy research, polling and news from across KFF about election-related health care issues.


CONTACT

Ann DeFabio

Senior Vice President and Chief Communications Officer

annd@kff.org

Total Run Time: 2:19

Total Run Time: 2:14

What Your Employer-Based Health Coverage Really Costs

Narrated by:

Published:

More Americans get health coverage through work than any other source — that’s more than 154 million people. And, the costs keep rising.

While employers bear most of that burden, workers also feel the pressure in the premium deductions in every paycheck and higher deductibles. 

The total premium for a family plan now averages $27,000 a year, according to KFF’s latest annual Employer Health Benefits Survey. That’s enough to buy a new Toyota Corolla Hybrid. Every. Single. Year.

KFF’s Matt Rae, Associate Director of the Program on the Health Care Marketplace, unpacks the full cost of employer-sponsored insurance and why that may be the bigger health care affordability story hiding in plain sight.


Watch and share the full series. Available on YouTube. 

KFF encourages linking to and reposting of our content on social media and other digital platforms.

Choose a video from our YouTube channel, click the Share button, select Embed, and copy the generated <iframe> code. Paste this HTML code directly into your websites editor or source code.

For collaboration or to request direct video downloads (vertical and horizontal formats) and carousel graphics, email us at outreach@kff.org

Subscribe to the KFF YouTube Channel. Stay connected with KFF on other social platforms

When citing us, please note our legal name is KFF. We should be cited as KFF, a nonprofit health policy research, polling, and news organization. Our name is no longer the Kaiser Family Foundation. More about KFF citations and permissions. 

The videos were scripted and produced by KFF. Visuals and graphics were developed using Adobe Creative Cloud with assistance from AI tools and refined by a graphic designer. Additional content: C-SPAN.


Video Transcript

Narrated by Matthew Rae, Associate Director, The Health Care Marketplace Program, KFF

More people get health coverage through an employer than from any other source. That’s 154 million Americans under the age of 65.

The debate over the Affordable Care Act’s expiring enhanced premium tax credits put health care affordability in the national spotlight.

But the issue doesn’t stop with Marketplace enrollees.

In the 2026 midterm election year, the cost of health care is a top economic worry for voters. 

And for good reason. The costs add up.

People who get health insurance through an employer typically see a deduction in every paycheck for their share of the premium.  

Workers contributed on average $6,850 towards the cost of a family premium in 2025. And, $1,440 for single coverage. 

And those payments are just the starting cost.

Most workers also have a deductible that must be met before insurance starts paying for most services. 

Workers at smaller companies, those with fewer than 200 employees, typically face higher out-of-pocket deductibles than those at larger companies.

As substantial as those out-of-pocket costs are, the true price tag of health insurance is largely shielded from workers through employer contributions, which on average cover about three quarters of the total premium. 

The total annual cost for a family plan, including both worker and employer premium contributions, has been steadily rising, now averaging about $27,000 a year. Up 26% from five years before.   

That’s enough to buy a new Toyota Corolla Hybrid. Every. Single. Year.

Rising premiums are straining both workers and employers.

The average annual earnings of a full-time worker was about $62,000. That puts the full cost of a family health insurance premium at over 40% of the typical salary.

Employers single out drug prices as a contributing factor, especially the widely popular and effective GLP-1 medication for diabetes and weight loss.

Add in rising hospital costs and a growing burden of chronic illness and the pressure isn’t letting up anytime soon.

Employer-sponsored insurance is a cornerstone of how Americans access health care. Understanding its full cost and what’s driving it higher matters for workers, employers, and policymakers alike.

MORE HEALTH POLICY VIDEOS

KFF video series titled "Are Health Insurers the Problem?" features a man in a suit shrugging with a confused expression, surrounded by illustrated symbols of loudspeakers, exclamation marks, and lightning bolts, suggesting debate or controversy. The YouTube logo is shown at the bottom left.

Series

Health in the 2026 Midterm Elections

This research is part of KFF’s Health in the Midterms series, a collection of policy research, polling and news from across KFF about election-related health care issues.


CONTACT

Ann DeFabio

Senior Vice President and Chief Communications Officer

annd@kff.org

Total Run Time: 3:00

Total Run Time: 3:00

Did the Affordable Care Act Make Health Care More Affordable?

Narrated by:

Published:

The Affordable Care Act (ACA) has been criticized for not living up to its name. But has it actually failed on affordability? The answer is complicated — and consequential. 

The ACA opened the door to comprehensive coverage for tens of millions who didn’t have that option before. In 2025, Marketplace enrollment hit an all time high of more than 24 million.

The expiration of the ACA’s enhanced premium tax credits at the start of 2026, combined with rising insurer premiums, put a spotlight on health care affordability that extends beyond Marketplace enrollees. 

KFF’s Cynthia Cox, Senior Vice President and Director, Program on the ACA and Peterson-KFF Health System Tracker, looks at the ACA’s record and the broader underlying question it raises:  what’s a fair price to pay for health care?


Watch and share the full series. Available on YouTube. 

KFF encourages linking to and reposting of our content on social media and other digital platforms.

Choose a video from our YouTube channel, click the Share button, select Embed, and copy the generated <iframe> code. Paste this HTML code directly into your websites editor or source code.

For collaboration or to request direct video downloads (vertical and horizontal formats) and carousel graphics, email us at outreach@kff.org

Subscribe to the KFF YouTube Channel. Stay connected with KFF on other social platforms

When citing us, please note our legal name is KFF. We should be cited as KFF, a nonprofit health policy research, polling, and news organization. Our name is no longer the Kaiser Family Foundation. More about KFF citations and permissions. 

The videos were scripted and produced by KFF. Visuals and graphics were developed using Adobe Creative Cloud with assistance from AI tools and refined by a graphic designer. Additional content: C-SPAN.


Video Transcript

Narrated by Cynthia Cox Senior Vice President, Program on the ACA Director, Peterson-KFF Health System Tracker, KFF 

The Affordable Care Act has been criticized for not living up to its name. But has it actually failed on affordability?

National health spending has been on the rise in recent years, driven by the increasing cost of hospital care, physician and clinical services, and prescription drugs. 

But looking back to the decade after the ACA, annual spending grew markedly slower. 

Dropping from average increases of 10 to 12 percent a year in the 1970s and 80s to around 4 percent in the 2010s.

It’s hard to prove that the ACA restrained spending, but there’s no evidence it accelerated growth even while helping to bring down the rates of the uninsured by providing coverage for millions more people.

The ACA allowed states to expand Medicaid to cover more low income individuals. It also created new Marketplaces where people without coverage through a job or other sources could buy their own insurance.

Now, the self-employed, small business owners, those between jobs or working without benefits, retirees not yet eligible for Medicare, can buy a comprehensive plan comparable to most employer-sponsored insurance.

The ACA also set new insurance regulations, among the most significant of which was prohibiting insurers from charging more or denying coverage based on a pre-existing health condition. 

It also established a list of essential health benefits that insurance must offer without lifetime or annual limits.

Importantly, the ACA’s individual market has similar average premiums as employer-sponsored plans. 

While employers offset the high cost of health insurance for workers, under the ACA, the federal government provides tax credits based on income to make self-purchased coverage more affordable. 

Even with these tax credits, the ACA faced criticism about not being affordable enough.

In 2021, Congress temporarily enhanced the ACA’s premium tax credits, and then extended them through 2025 as part of the Inflation Reduction Act, lowering out-of-pocket premium payments across the board for enrollees.

With coverage more affordable, Marketplace enrollment hit record highs.

The expiration of the enhanced premium tax credits at the end of 2025, combined with insurers charging more for coverage, means ACA Marketplace enrollees are facing higher costs this year. 

On average, up 58 percent, or about $780 more than last year. 

To offset the higher costs, many switched to lower premium plans. But that comes with a tradeoff: higher deductibles.

A KFF survey of ACA Marketplace enrollees found 3 in 10 switched plans in 2026, the large majority citing cost. Another 1in 10 dropped coverage altogether and are now uninsured.

While the expiration of the ACA’s enhanced premium tax credits has raised affordability concerns for many enrollees, the underlying question it raises is a wider reaching one: 

What is an affordable level of health care costs that people should be expected to bear?

MORE HEALTH POLICY VIDEOS

KFF video series titled "Are Health Insurers the Problem?" features a man in a suit shrugging with a confused expression, surrounded by illustrated symbols of loudspeakers, exclamation marks, and lightning bolts, suggesting debate or controversy. The YouTube logo is shown at the bottom left.

Series

Health in the 2026 Midterm Elections

This research is part of KFF’s Health in the Midterms series, a collection of policy research, polling and news from across KFF about election-related health care issues.


CONTACT

Ann DeFabio

Senior Vice President and Chief Communications Officer

annd@kff.org

Contraceptive Implants: Access and Coverage in the U.S.

Published: Jul 8, 2026

The contraceptive implant is the most effective reversible birth control method available. Implants, along with intrauterine devices (IUDs), are known as long-acting reversible contraception (LARCs) because they can be used to prevent pregnancy for several years and can be removed at any time. Implants have been available since the 1990s and have undergone substantial design modifications since their debut. The newest generation implant was introduced to the U.S. market in 2006 and remains the only contraceptive implant available in the U.S. Barriers to implant use include limited awareness and availability, high up-front costs for clinicians to stock the device, and required insertion and removal by a trained clinician. This fact sheet provides an overview of contraceptive implants including use, availability, and financing.

Background

In 1990, the Food and Drug Administration (FDA) approved Norplant, manufactured by Leiras Oy, the first subdermal contraceptive implant that was inserted under the skin of the upper arm by a trained clinician. Made of silicone, it had six capsules containing levonorgestrel, a synthetic hormone, and was effective for up to five years. Following concerns about its effectiveness and lawsuits on behalf of users who experienced complications, Norplant’s distributor, Wyeth-Ayerst, discontinued its U.S. distribution in 2002.

In 2006, the FDA approved Implanon, a single, thin, plastic, etonogestrel-releasing rod inserted under the skin of the arm. It is manufactured by Organon USA, a division of Merck. The improved design and composition made Implanon easier and faster to insert and remove than first generation implants. In 2010, the manufacturer replaced Implanon with Nexplanon, which is designed to be radiopaque (visible through x-ray) and has an improved insertion device. It is FDA-approved for use up to five years and prevents pregnancy by suppressing ovulation.

With a 0.05% failure rate, the contraceptive implant is the most effective FDA-approved reversible contraceptive. Additionally, the implant removes the potential for user error and non-use associated with self-administered contraception because it is inserted by a clinician and does not require any regular maintenance by the user.

Implants must be inserted and removed by a trained clinician who uses a special insertion device to place the implant just under the skin of the patient’s upper arm. Once inserted, the clinician ensures proper placement of the device by palpating the insertion site. The minor surgical procedure takes a few minutes and requires a local anesthetic and a small incision. After five years of use, the implant must be removed by a trained clinician, and if the patient desires, a new implant can be placed at that time. Implants may be removed by a clinician at any time before five years, and pregnancy can occur as soon as the first week following removal. 

Contraceptive implants are safe for most people and can be inserted any time if the user is not pregnant. Implants are primarily used for pregnancy prevention, but they can also be used to reduce menstrual cramps and make menstrual periods lighter. While there has been some concern about hormonal contraception for individuals who are breastfeeding, findings from the U.S. Selected Practice Recommendations for Contraceptive Use show that progestin-only methods, such as the implant, do not appear to negatively affect breastfeeding outcomes. Some common side effects include irregular menstrual bleeding, headache, weight gain, and breast pain, which may lead to discontinuation among some users. Although rare, some users who smoke or have certain health conditions may have a higher risk of developing severe complications.

Implant Use, Availability, and Awareness

Use

Because of their efficacy, continuation, and satisfaction rates, leading medical groups including the American College of Obstetricians and Gynecologists (ACOG) and the American Academy of Pediatrics have recommended the use of implants for most individuals of reproductive age, including adolescents and nulliparous and postpartum women. However, research demonstrates persistent misperceptions and a lack of awareness about implants. Although implant use in the U.S. has increased since it was first introduced in 1995, it is still lower than other contraceptive methods such as the IUD, pill, and sterilization.

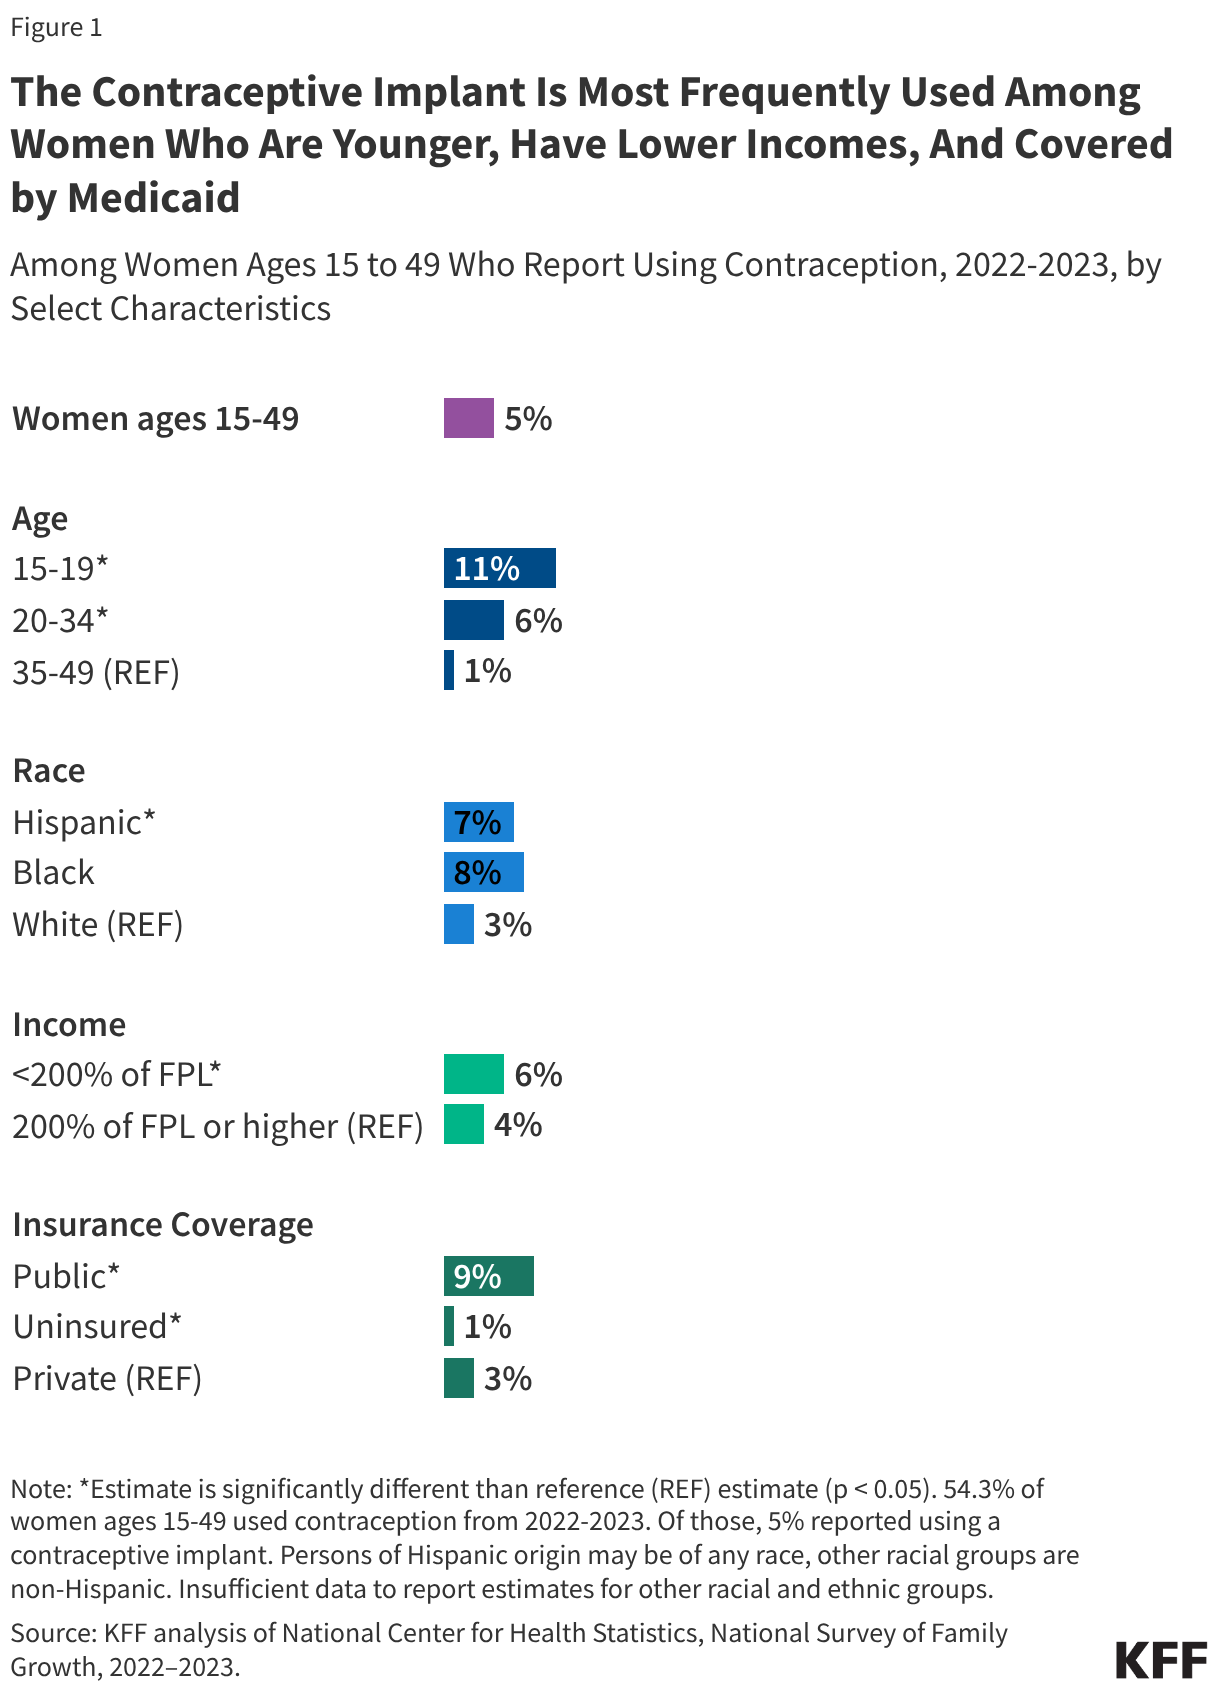
Between 2022 and 2023, the most recent years for which there are national data, 5% of women ages 15-49 who were currently using contraception used the implant (Figure 1). Implant users tended to be younger, lower-income, and covered by Medicaid. Notably, one in ten (11%) adolescent girls who use contraception report using the contraceptive implant compared to only 1% of women ages 35 to 49. Possible explanations for the association of higher implant use among younger women and lower-income women include the desire to avoid pregnancy for a longer period of time, lower maintenance and chance of user error, promotion of LARCs by medical organizations for adolescents, and availability at publicly funded clinics.

The Contraceptive Implant Is Most Frequently Used Among Women Who Are Younger, Have Lower Incomes, And Covered by Medicaid (Bar Chart)

Availability and Awareness

Access to implants can depend, in part, on the clinician’s ability and willingness to offer them. A 2023 KFF survey of OBGYNs found that eight in ten (83%) OBGYNs provided contraceptive implants in their practice. Publicly funded family planning clinics are an important source of care for many low-income and uninsured people of reproductive age. Access to contraceptive implants has been challenging for some clinics due to high upfront costs, as well as limited training and staff capacity to insert the device. As a result, some sites may be unable to provide the full range of contraceptive services to their patients, including contraceptive implants. Overall, 75% clinics offered implants from 2022-2023 compared to 61% in 2015.

Physicians may require multiple visits for a contraceptive implant insertion, which can be inconvenient for patients with limited time and resources. ACOG recommends OBGYNs implement same-day insertion procedures to improve patient access and experiences with contraceptive care, but some clinicians report barriers such as high upfront costs and challenges with reimbursement for contraceptive implants. Nonetheless, the share of publicly funded family planning clinics that offer same-day contraceptive implant insertions has increased overall. Between 2022 and 2023, about two-thirds (69%) of clinics performed same-day insertions, compared to one in three (37%) in 2015. 

In 2026, the FDA made some changes to the provision of implants. One change was the extension of the use of the implant from three to five years. Additionally, the FDA made the implant available only through the FDA’s Risk Evaluation and Mitigation Strategy program (REMS), a drug safety program with special requirements for clinicians, pharmacies, and other distributors who wish to provide the implant, due to the rare but serious health risks associated with improper insertion of the device. The Nexplanon REMS program requires clinicians to register with REMS, pass a specialized knowledge assessment, and complete an in-person 90-minute training from the manufacturer to become certified in Nexplanon insertion and removal. In addition to medical doctors, the training is open to advanced practice clinicians (such as nurses and physician assistants) who are authorized to perform implant insertions and removals in their practice jurisdiction. Additional clinical training for the implant is available from a variety of reproductive health organizations.

Insurance Coverage and Financing of Implants

The wholesale price for an implant is about $1275, in addition to potential costs associated with insertion and removal. The Affordable Care Act’s (ACA) contraceptive coverage requirement eliminated many women’s out-of-pocket costs for contraceptives, although some women still do not have access to full coverage.

There is currently no generic or therapeutically equivalent version of Nexplanon available in the U.S. Nexplanon’s manufacturer, Organon USA (a division of Merck), currently holds patents on the device and associated materials, though these patents are set to expire between 2027 and 2030.

Private Insurance

The ACA includes a requirement that most private insurance plans cover at least one type of all 18 FDA-approved contraceptive methods as prescribed without cost sharing. This means that most private plans must cover the implant at no cost to policy holders. Before the ACA was passed, individuals with private insurance were likely to face out-of-pocket expenses for the implant and associated visits. After the contraceptive coverage mandate went into effect in 2012, research found that about three in four (73%) women with private insurance paid $0 in out-of-pocket expenses for contraceptive implants in 2020, compared to about three in then (28%) in 2012. However, recent research suggests an increase in the number of women with out-of-pocket expenses for contraceptive implant insertion, despite the coverage requirement. While nearly two-thirds (64%) of women with private insurance continued to have no out-of-pocket expenses for contraceptive implant insertion, over one in three (36%) paid a median cost of $16.88 for implant-related services in 2023—including office visits, ultrasounds, medications, and STI and pregnancy testing. Nonetheless, studies have found an increase in LARC initiation overall among women with private insurance coverage since the ACA’s coverage requirement took effect.

Insurers can use medical management to help control costs and encourage beneficiaries to choose more affordable contraceptive methods, but federal guidance prohibits insurers from categorically restricting access to a particular contraceptive method. Insurers can choose to cover generic contraceptives while charging cost-sharing for the brand-name version. Since contraceptive implants do not have a generic equivalent, the brand-name version (Nexplanon) must be covered without cost-sharing.

Medicaid

Federal law requires Medicaid programs to cover family planning services and supplies without cost sharing, but there are variations in coverage between states and between different Medicaid populations. For enrollees of the traditional Medicaid programs that were in place prior to the passage of the ACA, coverage of implants is determined by each state program. Recognizing the high (cost) effectiveness of LARCs, many states are pursuing policies to reduce barriers to provision, like reimbursing for insertion and removal, returning unused devices for credit, and providing hospitals with separate payments for post-partum LARC insertion.

Those who qualify for Medicaid under the ACA’s expansion of the program must receive coverage for the implant because the ACA requires these expansion programs to cover all FDA-approved methods for women without cost sharing, which is the same as the requirement for private insurance plans. Furthermore, 30 states and D.C. extend Medicaid coverage for family planning services, including contraception, to some uninsured women who do not qualify for full scope Medicaid.

Uninsured

The federal Title X Family Planning Program funds a network of clinics to provide family planning care to millions of low-income and uninsured people at reduced or no cost. Federal guidelines such as the Office of Population Affairs’ and the CDC’s Providing Quality Family Planning Services (QFP) and the Health Resources and Services Administration’s (HRSA) recommendations for women's preventive services state that offering women the full range of FDA-approved contraceptive methods is a crucial aspect of quality family planning services.

Research shows that sites that received Title X funds were consistently more likely to offer contraceptive implants compared to sites that do not receive Title X funding. Community health centers (CHCs) and specialized family planning clinics such as Planned Parenthood centers play a critical role in providing reproductive health care to low-income people, medically underserved communities, and people who are uninsured. CHCs are required to provide “voluntary family planning” services but have significant leeway in determining the specific services they provide. For example, nearly all (98%) Planned Parenthood clinics offered same-day implant insertions from 2022 to 2023, compared to just over half (57%) of federally qualified health clinics.

As a result of the 2025 One Big Beautiful Bill Act and other federal policy changes, the uninsured rate is expected to rise substantially over the next decade. Uninsured women could decide to stop using contraception because they cannot afford it or switch to a less effective method, which could result in an increase of unwanted pregnancies and a loss of reproductive autonomy. KFF research has found that one in five uninsured women of reproductive age has had to stop using a birth control method in the past 12 months because they couldn’t afford it, a rate that is four times greater than those with Medicaid (5%) or private insurance (2%).

News Release

In Preliminary Rate Filings, ACA Marketplace Insurers Largely Propose Double-Digit Premium Increase For 2027, Following a Steep Climb This Year 

Premiums Could Jump More Than One-Third Over Two Years—Middle-Income Enrollees Face the Full Costs Without Enhanced Credits, Even as Existing Federal Subsidies Shield Most from Further Increases

Published: Jul 8, 2026

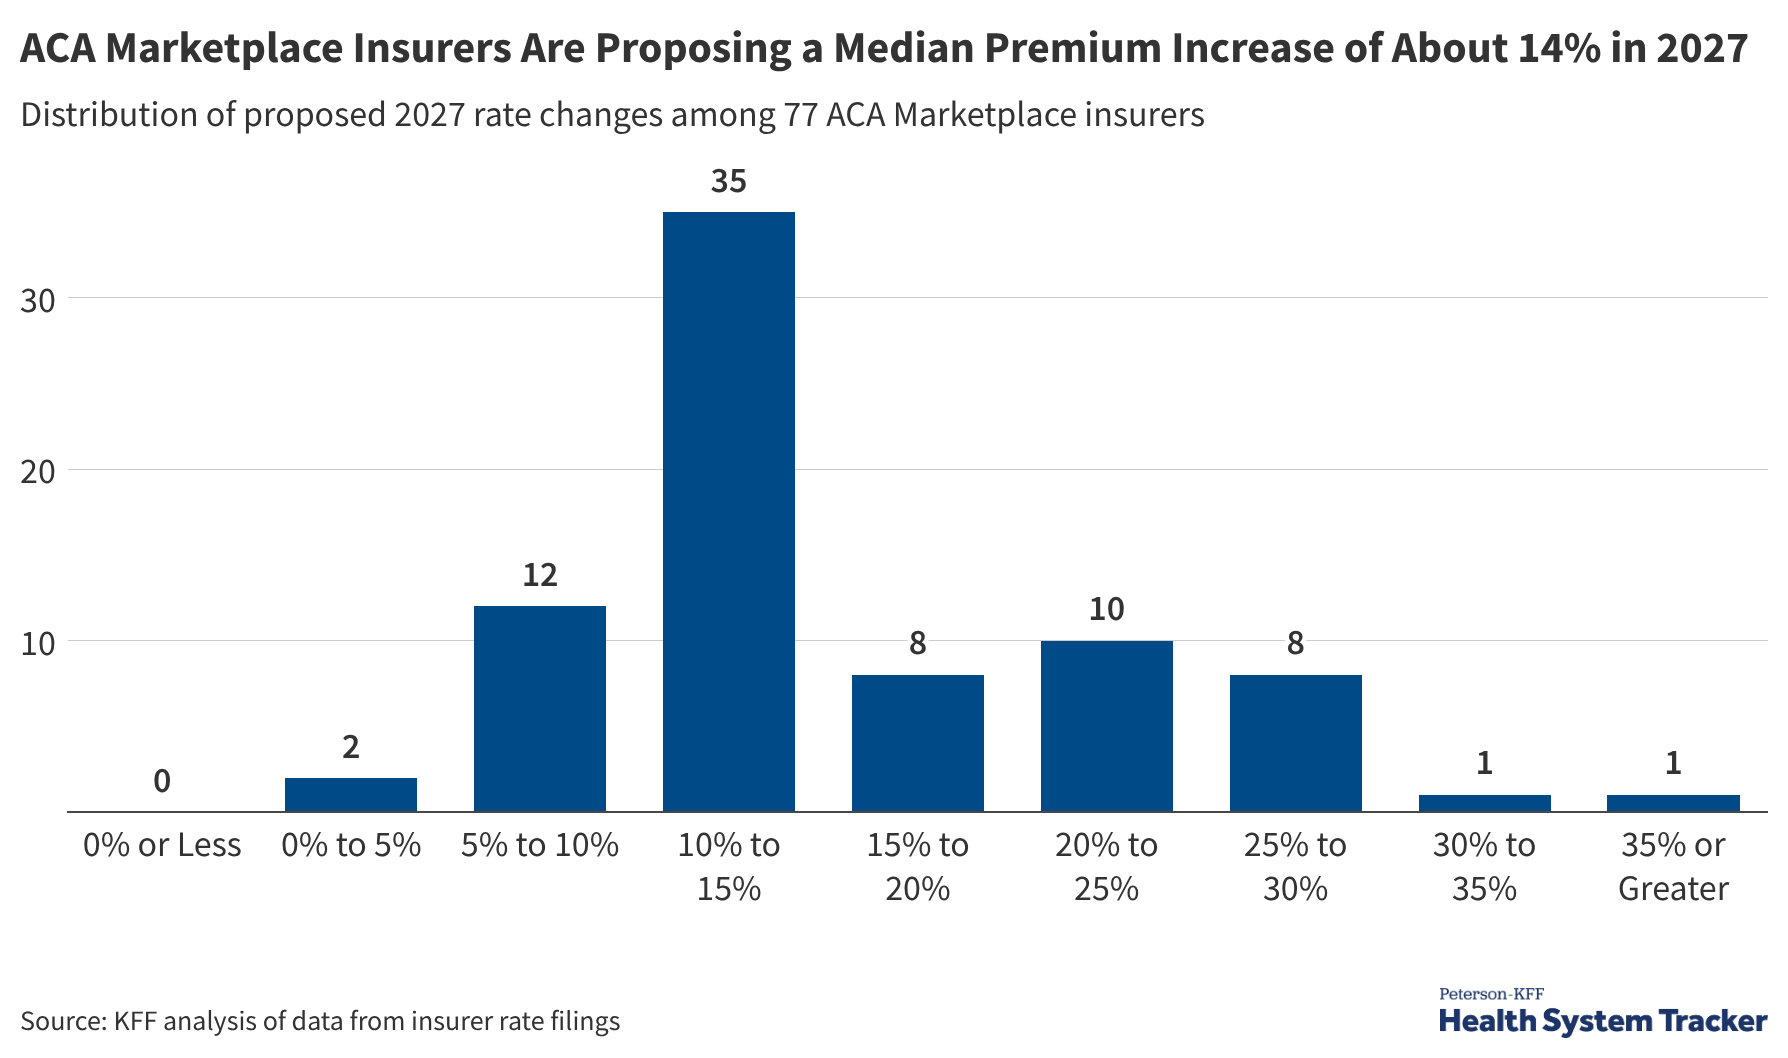
ACA Marketplace insurers are proposing a median premium increase of 14% for 2027— indicating a likely second consecutive year of double-digit increases, according to a new analysis of preliminary rate filings in 16 states and DC. If these increases hold, typical premiums for insurers participating in the ACA Marketplaces would jump by more than one-third between 2025 and 2027.

Across the 77 ACA Marketplace insurers in the 16 states and DC that have submitted rate filings so far, most are requesting premium increases of between 10% and 20% for 2027, with 20 insurers requesting premium increases of more than 20%.  

July 15 is the deadline for health insurance companies to submit their proposed premiums for 2027 ACA Marketplace plans. These preliminary filings provide insight into the factors insurers expect to drive health costs for the coming year. Among the key drivers, insurers cite the rising cost of health services, the expiration of the enhanced premium tax credits, and some federal regulatory changes.

  • The rising cost of health services have been driven by the cost of hospitalizations, physician visits, and prescription drugs—including GLP-1s and other specialty medications. Relatedly, labor shortages and general economic inflation have driven up provider wages and costs, increasing the cost of health services as well. The underlying cost of medical care and prescription drugs has risen by 10% for 2027—greater than the 8% average growth seen over the last few years.
  • The ACA’s enhanced premium tax credits expired at the end of 2025—leading to a 58% average increase in out-of-pocket premiums in 2026 and deductibles of about $1,000 more per person. Most Marketplace enrollees are largely protected from the premium increases because they still qualify for ACA subsidies, though at a lower level. However, people with incomes at 400% or more of the federal poverty level ($62,600 for a single person in 2026) lost subsidies entirely when the enhanced credits expired and, therefore, face the full increase in premiums. This caused many healthier enrollees to leave the ACA Marketplaces in 2026, leaving behind a smaller number of enrollees who are somewhat sicker and more expensive to cover on average. Further market deterioration is expected heading into 2027. Insurers estimate that the sicker risk pool drove 2026 premiums up by roughly four percentage points and expect another four percentage point increase in 2027.
  • Federal regulatory changes, including the recent Notice of Benefit and Payment Parameters and the Marketplace Integrity and Affordability Rule, have also been cited as having an upward effect on premiums.  

The full analysis and other data on health costs are available on the Peterson-KFF Health System Tracker, an online information hub dedicated to monitoring and assessing the performance of the U.S. health system.

Digital Health Tools and Technologies: An Overview of CMS’ Recent Efforts to Expand Their Use in Medicare

Authors: Nancy Ochieng, Juliette Cubanski, and Tricia Neuman
Published: Jul 7, 2026

As an increasing share of older adults have adopted digital health technologies over the past several years, and with most expressing interest in using them to manage their health care, the Centers for Medicare & Medicaid Services (CMS) has introduced several initiatives to expand the use of digital health technologies in Medicare. Broadly speaking, these technologies include health-related applications (“apps”), online patient portals, and connected devices such as smartphones and wearable devices that can be used to measure or track health data.   

A central component of CMS’s efforts in this area is the Health Tech Ecosystem, launched in 2025, through which CMS partners with private-sector organizations, including health care providers, payers, health app developers, and electronic health record vendors, to increase the availability of digital health tools and improve access to and exchange of electronic health information. While the initiative spans all CMS programs, people with Medicare gained access to the first wave of personalized health apps through the new Medicare app Library launched in April 2026, which allows beneficiaries to access third-party apps that have undergone independent review and meet certain requirements for privacy and security.

Separately, CMS introduced the ACCESS Model, a new Center for Medicare and Medicaid Innovation payment model scheduled to begin in July 2026 that aims to expand access to technology-enabled care for people in traditional Medicare with certain chronic conditions. CMS also enhanced the Medicare Plan Finder, the official online tool on Medicare.gov that helps beneficiaries compare and select Medicare coverage options.

This brief summarizes these digital health initiatives and draws on data from various surveys, including KFF Tracking Polls from September 2025 and March 2026, to highlight facts about recent experiences with and use of digital health tools among Medicare beneficiaries and older adults more generally.

The CMS Health Tech Ecosystem Aims to Expand Access to Patient-Facing Apps and Improve Health Data Exchange  

As part of the CMS Health Tech Ecosystem, dozens of companies have pledged to develop patient-facing apps that support exchange of health data and enable connectivity to the new Medicare App library, where people with Medicare can access third-party apps that meet CMS’s privacy and security criteria. To support the use of these tools, participating app developers, health information networks, electronic health record vendors, and payers have agreed to adopt common standards that make it easier for patients and providers to access and exchange electronic health information through the apps. The Medicare App library that launched in April 2026 will feature apps that meet one of the following initial use cases:

  • Supporting management and prevention of diabetes and obesity, such as features that enable medication management or include resources related to prediabetes.
  • Integrating conversational artificial intelligence (AI) assistants to help people navigate their care options and manage aspects of their health care, such as checking symptoms.
  • Allowing patients to securely share their health and identity information electronically at check-in instead of completing paper forms (so-called “kill the clipboard” apps). Patients can also receive a summary of their visit through the same platform.

As of June 2026, the Medicare app library lists five apps that are available to beneficiaries and an additional eight apps that are expected to be added soon. A search tool on the app library website enables a comparison of apps based on 13 key features, such as managing health records, connecting to wearable devices, or sharing information with caregivers or providers, as well as searching for apps tailored to a range of health conditions and by price, with some apps being free and others requiring a subscription or having paid features.

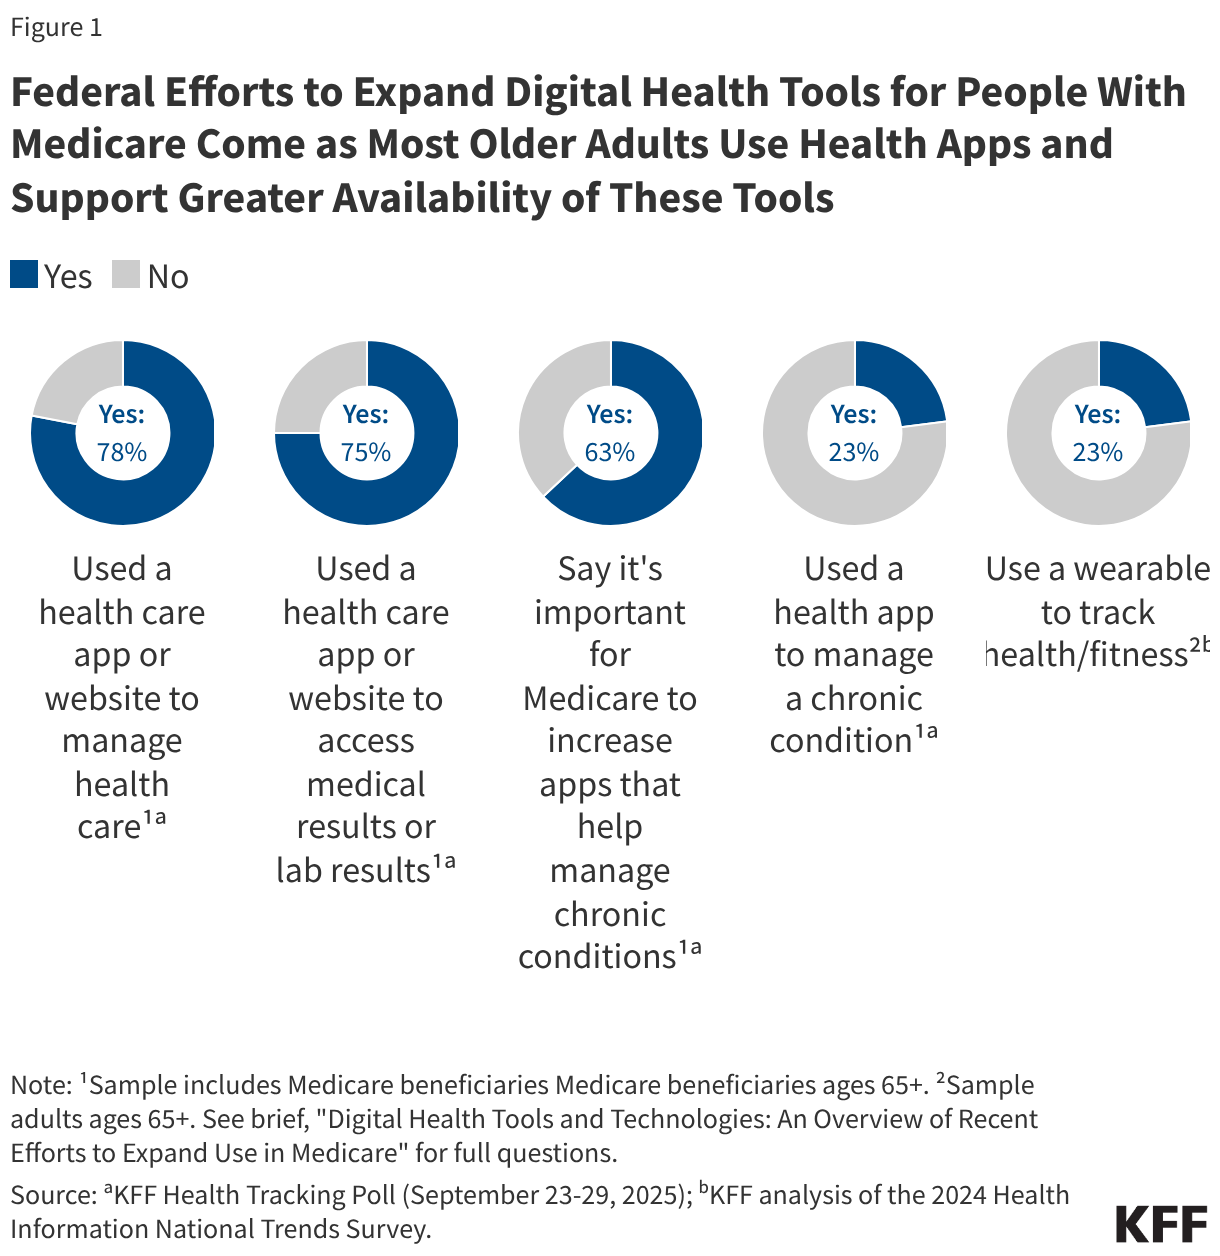
CMS’s efforts to expand the availability of health care apps that have been vetted by the agency and meet specified standards for privacy and security build on the popularity and appeal of these tools, including among older adults.In 2025, eight in 10 (78%) Medicare beneficiaries ages 65 and older used a health care app or website to manage their health care in the past year, and more than half (58%) said these tools make managing their health care easier, according to a September 2025 KFF Health Tracking Poll (Figure 1). Three-quarters (75%) say they have used a health care app or website to access their medical records or lab results, the most common reported use of health apps among Medicare beneficiaries.

In addition, nearly two-thirds (63%) of older adults on Medicare say it’s important for Medicare to increase the availability of apps that help manage chronic conditions with the help of a health care provider, but few older adults on Medicare—about one in four (23%)— say they have used a health app or website in the past year to manage a chronic condition with their health care provider.

Federal Efforts to Expand Digital Health Tools for People With Medicare Come as Most Older Adults Use Health Apps and Support Greater Availability of These Tools (Small multiple donut chart)

The ACCESS Model Expands Access to Technology-Enabled Care for People in Traditional Medicare with Certain Chronic Conditions

The CMS Innovation Center launched the ACCESS Model in December 2025 to test a national, voluntary payment approach that uses technology-supported care options to help traditional Medicare beneficiaries prevent and manage a specified set of chronic conditions. These chronic conditions are grouped into an initial set of four clinical tracks, two of which target cardiovascular, kidney, or metabolic conditions (e.g., hypertension, diabetes), one that targets musculoskeletal conditions (e.g., chronic musculoskeletal pain), and another that targets behavioral health conditions (e.g., depression). About 7 in 10 Medicare beneficiaries have conditions that qualify for at least one track, though this estimate may change as CMS considers additional conditions and clinical tracks in the future.

The model is voluntary for both participating organizations and people in traditional Medicare, who need to enroll directly with participating organizations or through a referral from their provider. It will run for 10 years from July 2026 through June 2036, with organizations joining in cohorts on a rolling basis throughout the model period. Medicare beneficiaries may disenroll or switch participating organizations after 90 days of their enrollment, and participating organizations may withdraw with advance notice to CMS and beneficiaries. 

To date, 190 organizations have been accepted as participants, including digital health companies, mental health organizations, health systems, and physician groups, most of which, according to CMS, have not previously served Medicare beneficiaries. These participants, who must enroll as Medicare Part B providers or suppliers, will receive monthly payments for managing beneficiaries’ qualifying conditions, with full payment tied to achieving certain health outcomes, such as helping a beneficiary with hypertension lower their blood pressure to a specific level. Currently, the vast majority of accepted applicants (151 organizations) have signed up for at least one of the two tracks focused on cardiovascular, kidney, or metabolic conditions, while 108 have signed up for the track on behavioral health conditions and 76 for the musculoskeletal track. Because organizations can participate in multiple tracks, these categories are not mutually exclusive.

Currently, it is unclear how broadly individual participants will operate geographically or the scope of services offered by each participant. CMS plans to launch a public directory of all ACCESS participants in July 2026, allowing people with Medicare and their providers to identify participating organizations, the conditions they treat, with risk-adjusted outcome measures for each organization expected to be added beginning in 2028. Organizations that participate in the model and also pledge to join the Health Tech Ecosystem will also be featured in the Medicare App Library as participants.

Participating organizations may use a variety of digital tools to deliver services under the Model, ranging from FDA-regulated medical devices such as continuous glucose monitors, to mobile applications, wearables, and non-FDA regulated software. CMS gives participants flexibility in selecting technologies and clinical tools that support the model. Some tools may be classified as clinical devices, including continuous glucose monitors, blood pressure cuffs, and wearable devices such as fitness trackers and smartwatches. Beneficiaries may receive these tools on either a loan or ownership basis from the participating organization or use their own devices. While participants generally may not require beneficiaries to purchase or rent devices classified as clinical, beneficiaries may still need access to non-clinical technologies, such as internet access, tablets, or smartphones to use technology-enabled services.

Variation in the technologies used under the ACCESS Model, as well as Medicare beneficiaries’ access to and familiarity with digital tools, may lead to differences in how people in traditional Medicare access and experience technology-supported care under this model. For example, some beneficiaries may enroll with participating organizations that incorporate the use of technologies already integrated into their care, such as Medicare-covered continuous glucose monitors. Others may enroll with participating organizations that incorporate technologies such as wearable fitness trackers that are generally not covered by Medicare and may be less widely adopted among beneficiaries. For example, in 2024, just under a quarter (23%) of adults ages 65 and older used an electronic wearable device to monitor or track their health or activity in the past year, based on KFF analysis of the Health Information National Trends Survey (Figure 1).  However, among older adults who use wearable devices, the vast majority (85%) said they would be willing to share data from their device with their health care providers.

Medicare Advantage enrollees, who account for more than half of all Medicare beneficiaries, do not qualify for the ACCESS Model, but 16 insurers, including those serving Medicare Advantage enrollees, have pledged to adopt similar models of care to date. Many Medicare Advantage enrollees report having conditions being targeted by the ACCESS Model, including hypertension (64%), diabetes (35%), and depression (28%), based on a KFF analysis of the 2023 Medicare Current Beneficiary Survey (MCBS). Because details about the programs pledged by the 16 insurers are not yet available, it is unclear how they will be structured or the patient populations that will be targeted, though they may resemble existing supplemental benefits offered by Medicare Advantage plans. In 2026, 44% of enrollees are in individual Medicare Advantage plans that offer remote access technologies, which may include clinical devices such as continuous glucose monitors, and 95% are in plans that offer fitness benefits, which may include discounts on wearable devices. For example, some plans offered by Devoted Health, which has pledged to align with ACCESS, offer partial reimbursement for the purchase of a wearable device as part of a fitness benefit. While CMS collects data on use and spending on supplemental benefits in Medicare Advantage plans, such as the number and characteristics of enrollees who use these benefits, this data is currently unavailable to researchers and consumers.

Changes to the Medicare Plan Finder Could Make It Easier to Compare and Select Medicare Coverage Options

In 2025, CMS announced enhancements to the Medicare Plan Finder, the official tool on the Medicare.gov website that helps beneficiaries compare and select Medicare coverage options. These enhancements include the following updates: 

  • Offering Medicare Advantage provider directory information to help beneficiaries identify whether their doctors are in a plan’s network. Unlike traditional Medicare, most Medicare Advantage insurers use provider networks, which can change from year to year. Medicare beneficiaries say having access to their preferred providers is an important factor when selecting their Medicare coverage, yet in 2022, Medicare Advantage enrollees were in a plan that included just under half (48%) of all physicians available to traditional Medicare beneficiaries in their area. Prior to 2025, the Medicare Plan Finder did not include data on provider networks, resulting in beneficiaries’ going to each plan’s website or third-party sources to determine whether their preferred providers were in the network. Incorporating provider directory information in the Medicare Plan Finder may make it easier for beneficiaries to evaluate their coverage options, though the usability and completeness of this feature continue to evolve.
  • Showing additional details on more than 30 supplemental benefits under Medicare Advantage. These details include in-network and out-of-network cost sharing amounts, whether prior authorization is required for each benefit, and whether there are limits on how much the plan will provide. Currently, most Medicare Advantage enrollees are in plans that offer supplemental benefits not covered by traditional Medicare, such as vision, hearing, and dental, and beneficiaries highlight the availability of extra benefits as a reason they choose to enroll in Medicare Advantage plans.

CMA also announced the launch of an “AI-powered” prescription drug search tool that will provide personalized cost comparisons across pharmacies. While prescription drug costs covered under Medicare Part D, including premiums and deductibles, can change from year to year and vary by plan, most enrollees in Medicare Advantage prescription drug plans (81%) and stand-alone prescription drug plans (69%) in 2023 did not compare their plans’ drug coverage with drug coverage offered by other plans in their area. According to CMS, the new prescription drug search tool will be available on Medicare.gov to users with an individual account but will not be incorporated in the Medicare Plan Finder. This tool could provide more individualized guidance to help Medicare beneficiaries lower their prescription drug costs beyond the prescription drug lookup tool that is already incorporated in the plan finder.

However, these enhancements will require beneficiaries to access the Medicare website and navigate the plan finder, even as just over half (53%) of Medicare beneficiaries said they hadn’t visited the Medicare website, according to KFF analysis of the 2023 MCBS, and it is unknown how many beneficiaries have used the Medicare Plan Finder specifically to compare coverage options or enroll in a plan. But with less than a third (28%) of Medicare beneficiaries comparing their coverage options during a previous open enrollment period for Medicare, enhancements to Medicare Plan Finder and Medicare.gov may help address some of the challenges beneficiaries face when evaluating their coverage options and comparing costs.

The Business of Health with Chip Kahn

AI: Rewiring the Machine

July 7, 2026

Video

Audio

About this Episode


Episode 11, AI Series: In a conversation focused on the technology underlying AI in health care, Chip is joined by Seema Verma, former administrator of the Centers for Medicare & Medicaid Services (CMS), and now Executive Vice President and General Manager at Oracle Health and Life Sciences, the second largest electronic health records (EHR) platform in the U.S. Seema shares her insights on the evolution of EHRs and why it’s necessary to redesign these systems to better integrate AI capabilities and improve the quality of care.

The Host


Headshot photo of Chip Kahn wearing a navy blue suit with a red tie, red pendant on lapel, and glasses.

Sr. Visiting Fellow

Charles N. Kahn III is a senior visiting fellow at KFF. He is also a visiting senior fellow at the American Enterprise Institute and a nonresident senior scholar at the University of Southern California’s Schaeffer Center for Health Policy & Economics. He serves as co-chair of the international Future of Health collaborative.

Guest


Executive Vice President and General Manager, Oracle Health and Life Sciences

Seema Verma is Executive Vice President and General Manager of Oracle Health and Life Sciences, leading global strategy to modernize healthcare through data, connectivity, and AI. Previously, she served as Administrator of the Centers for Medicare & Medicaid Services.  

A recognized industry leader, she serves on multiple healthcare boards and has been named among Modern Healthcare’s Most Influential People and Becker’s Healthcare’s Great Leaders in 2026. She has a bachelor’s degree in life sciences from the University of Maryland and a master’s degree in public health from John’s Hopkins University. 


SERIES

This weekly podcast features insightful conversations between host Chip Kahn and his guests, who discuss the business of health care, connecting the dots between the health care business, policy, and patients.

The podcast’s first series on AI in health care illuminates how AI is changing health care, and features guests who are deploying this technology, managing its consequences, and designing policy around it.