Medicaid’s Home Care Support for Family Caregivers in 2026
Key Questions
KFF estimates that 5.3 million Medicaid enrollees use home care, which provides medical and supportive services to help people with the activities of daily living (such as eating and bathing) and the instrumental activities of daily living (such as preparing meals and managing medications). Medicare generally does not cover home care (also known as home- and community-based services, or HCBS), and Medicaid paid for two-thirds of home care spending in the U.S. in 2023.
In Medicaid home care, many people “self-direct” their services, giving them greater autonomy over the types of services provided and who they are provided by and, in some cases, allowing payments to family caregivers. Payments for caregiving can help mitigate the financial struggles family caregivers experience when they are forced to reduce their hours of work or quit their jobs on account of their caregiving duties. KFF focus groups of caregivers found that family caregivers often reported struggling to make ends meet and having to reduce the hours they work at other jobs due to the demands of caregiving. A 2026 AARP Caregiving Out-of-Pocket Costs study found that the costs of caregiving are nearly one third of average household incomes and are even higher for lower income individuals and those with complex care needs. Self-directed services can also help address shortages of paid home care workers, which can be one of the factors placing additional strain on family caregivers. Beyond paying for their caregiving, Medicaid supports family caregivers with services such as training, support groups, and respite care (which is paid care that allows family caregivers to take a break from their normal responsibilities).
Heading into 2027, there are multiple factors pressuring states to reduce Medicaid supports for family caregivers, including slower state revenue growth, substantial changes to Medicaid financing from the 2025 reconciliation law, and the federal government’s efforts to address Medicaid program integrity, including a focus on home care (with paused federal reimbursement for some home care programs in two states). Although program integrity efforts have focused on provider organizations potentially engaged in fraud, the delivery of services in people’s homes and payments to family and friends, who are not otherwise registered as Medicaid providers, has increased scrutiny over Medicaid supports for family caregivers. In response, recent tracking of programmatic changes to Medicaid home care shows several proposed cuts were to programs supporting family caregivers.
Amidst this background, this issue brief describes the availability of self-directed services and supports for family caregivers in Medicaid home care in 2026. The data come from the 24th KFF survey of officials administering Medicaid home care programs in all 50 states and the District of Columbia (hereafter referred to as a state), which states completed between April and August 2026. The survey was sent to each state official responsible for overseeing home care benefits (including home health, personal care, and waiver services for specific populations such as people with physical disabilities). All states except Florida and South Carolina responded to the 2026 survey, but response rates for certain questions were lower. South Carolina’s responses to the 2025 survey were included with their permission. Survey findings are reported by state and waiver target population, although states often offer multiple waivers for a given target population. Key findings include:
- All responding states except Alaska allow Medicaid enrollees to self-direct their home care in at least some circumstances, and among those states, all allow enrollees to select, train, and dismiss their caregivers and set caregiver worker schedules.
- All responding states pay family caregivers under some circumstances and provide family caregivers with other types of support, including respite care (Figure 1).
- Family caregiver supports are most widely available for caregivers of people with intellectual or developmental disabilities (I/DD).
- Despite concerns about cuts to Medicaid supports for family caregivers, in 2026, most supports stayed the same as in the prior year, and a few states increased their supports.
How Many States Allow Medicaid Enrollees to Self-Direct Their Home Care?
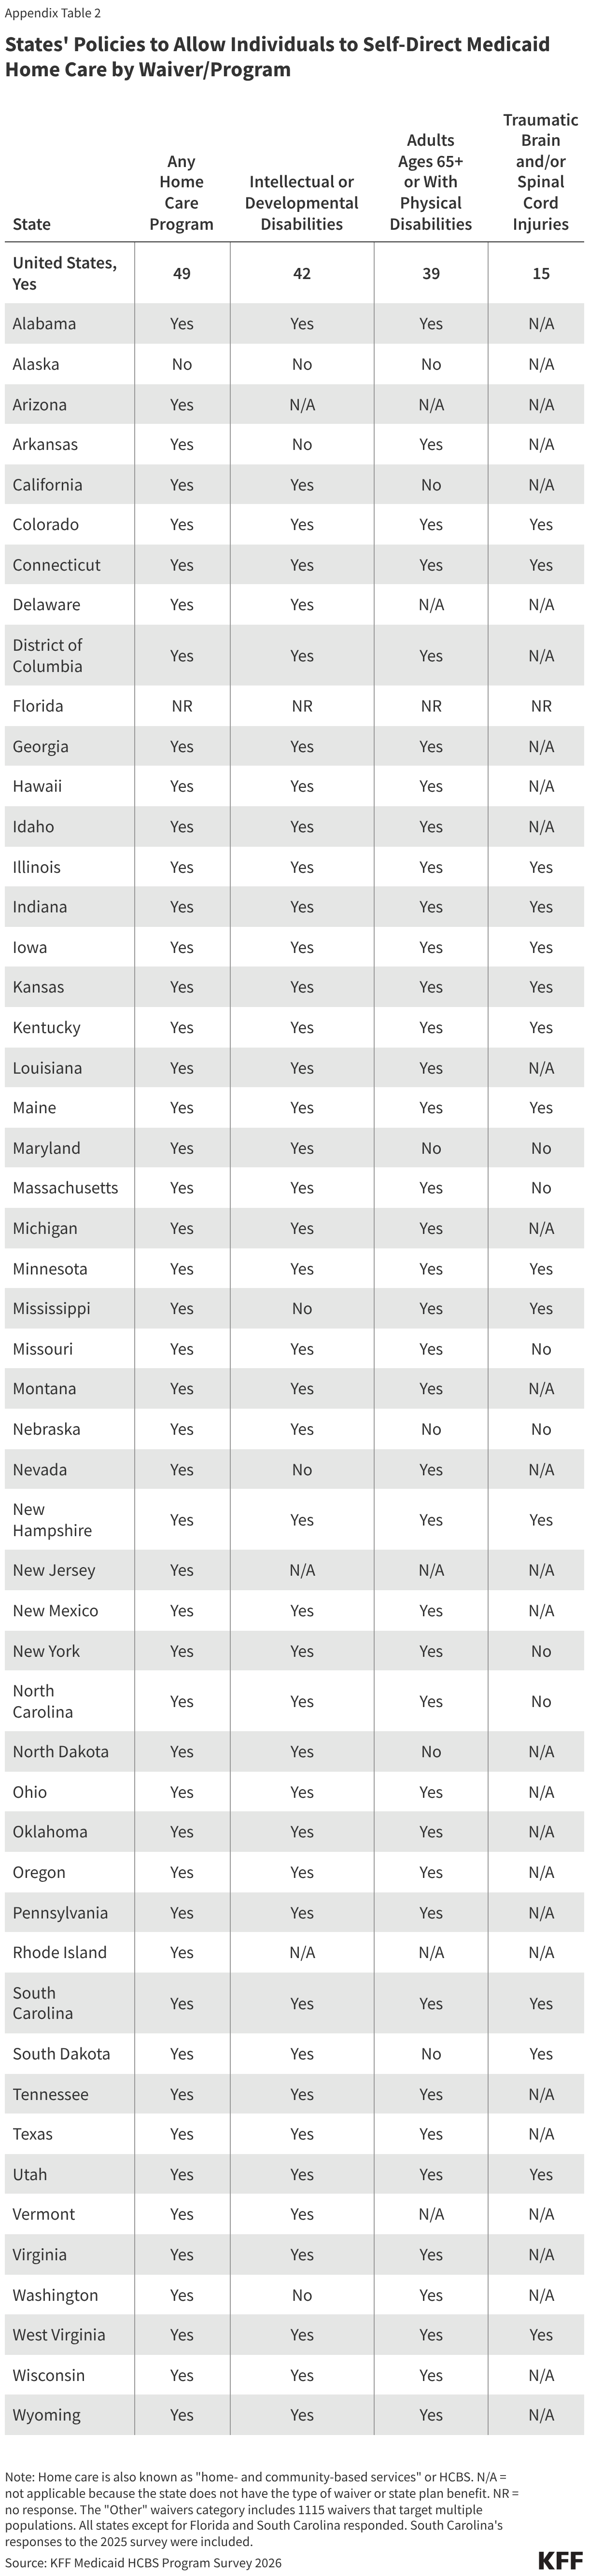
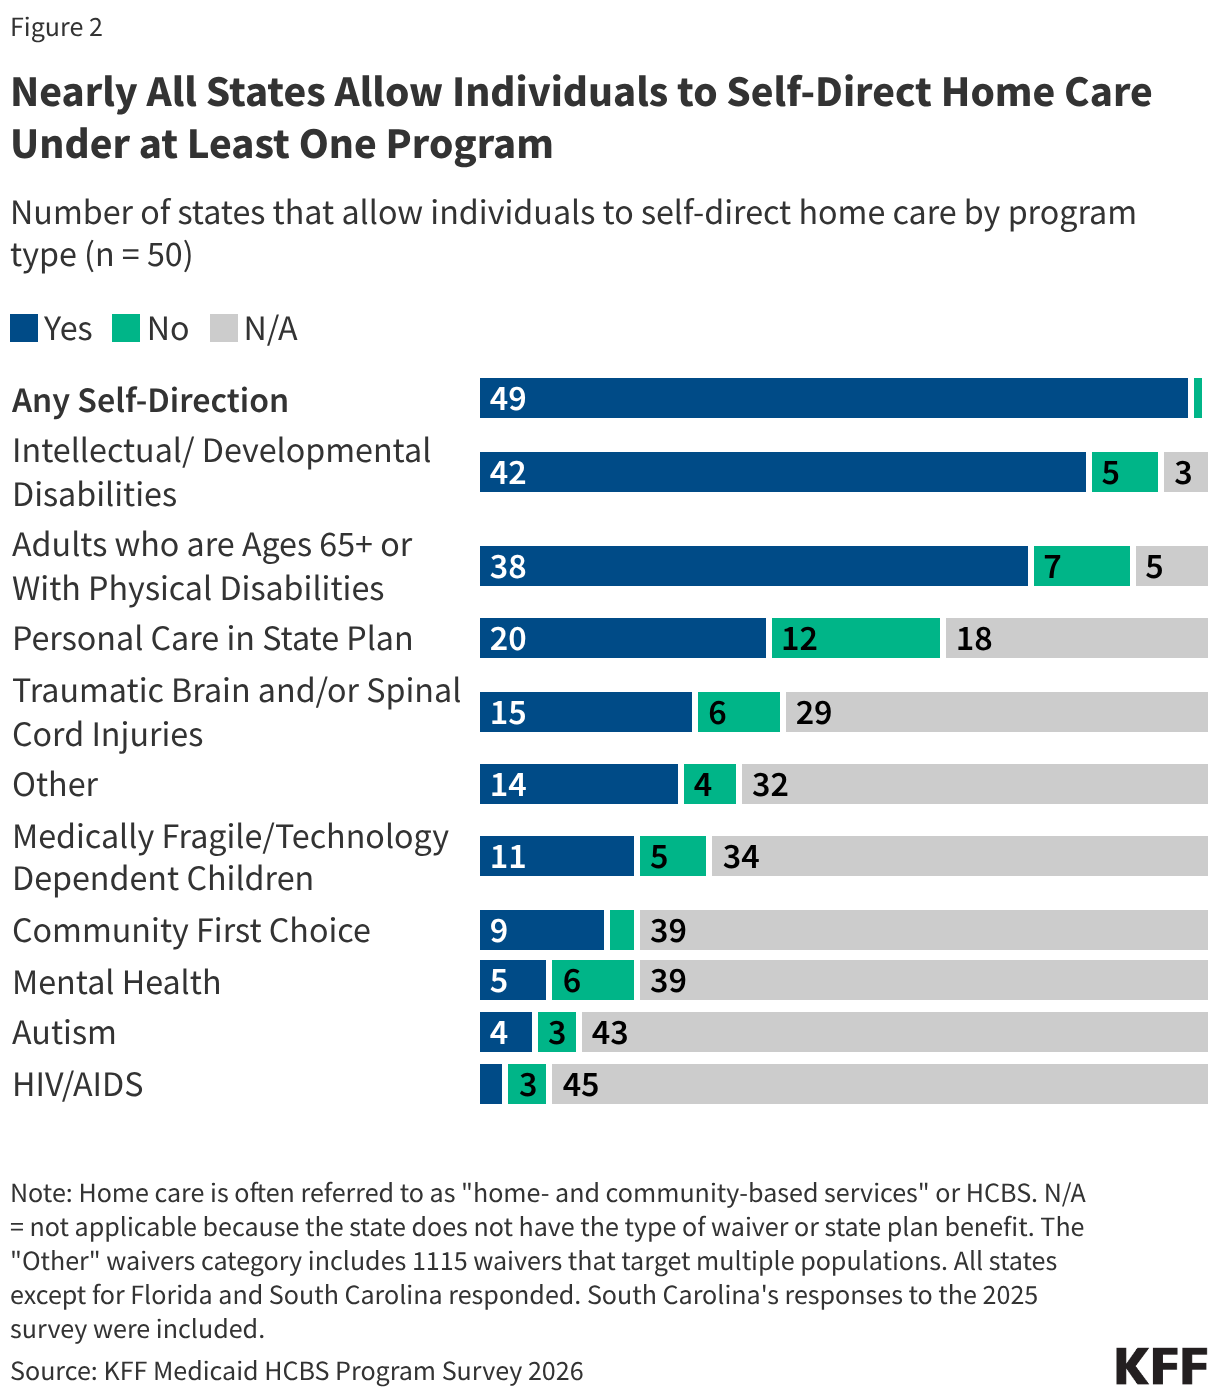
Nearly all states allow Medicaid enrollees to self-direct their home care in some circumstances (Figure 2, Appendix Table 2). Self-direction came out of the “consumer-directed” movement for personal care services that started with demonstration programs in 19 states, funded through grants from the Robert Wood Johnson Foundation. Today, states may give people the option to self-direct home care through a wide variety of optional home care programs. States most frequently allow self-direction in waivers that serve people with I/DD, followed by adults ages 65 and older or those with physical disabilities. Among the 50 states responding to KFF’s survey, Alaska is the only state that reported not permitting self-direction under any of its home care programs.
While all responding states, except Alaska, allow self-direction under at least one waiver or program, some states expanded self-direction in specific waivers or programs between 2025 and 2026. Four states newly allowed self-direction in 2026: Indiana, in its waivers for people with I/DD and for people with traumatic brain and/or spinal cord injuries; New York, in its waivers for adults ages 65 and older and people with physical disabilities; New Mexico, in its waiver for medically fragile and technology-dependent children; and D.C., under its state plan personal care benefit.
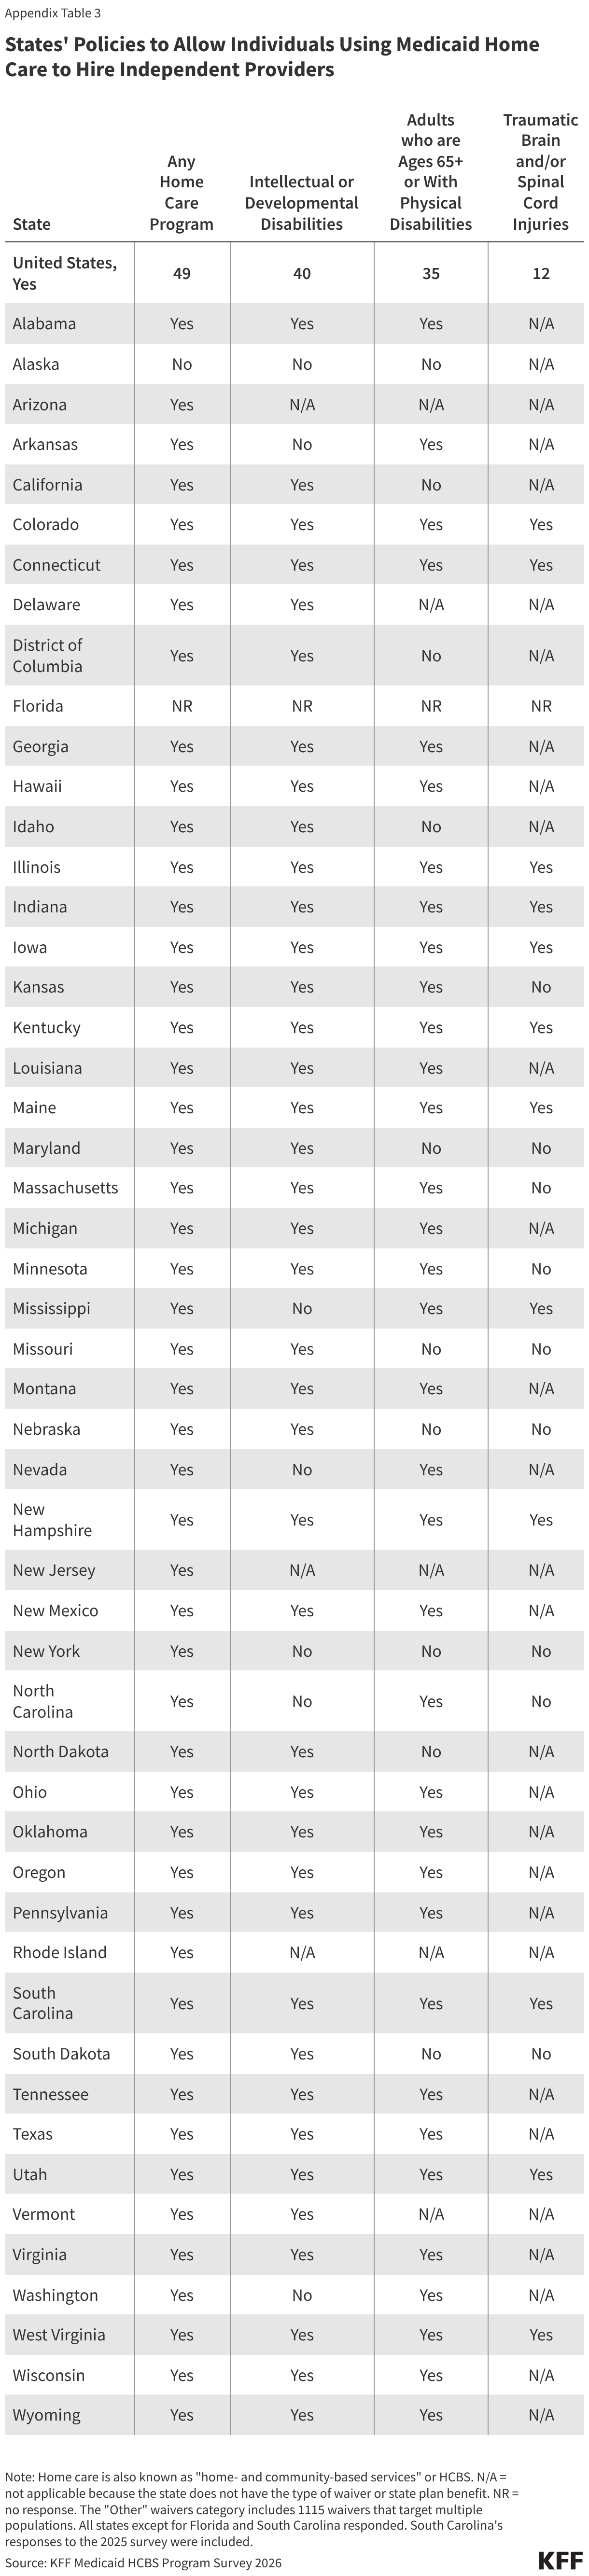
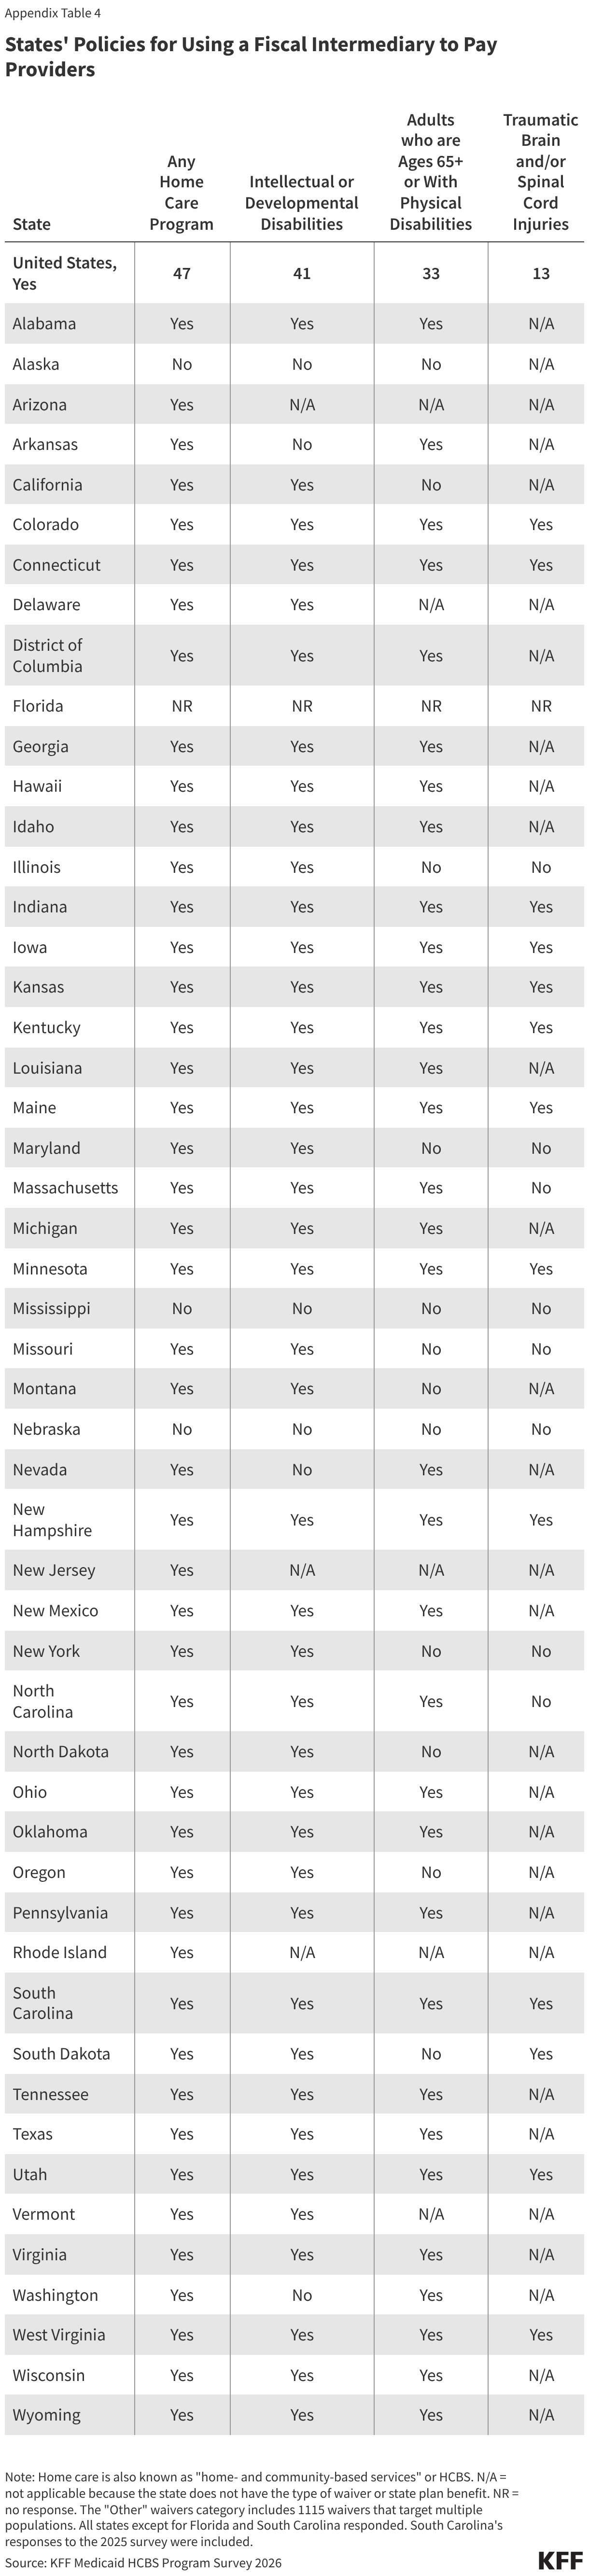
Among states that authorize self-direction, all states allow enrollees to select, train, and dismiss workers and set caregiver worker schedules (Figure 3, Appendix Table 3, Appendix Table 4). The ability to select, train, and dismiss workers is referred to as “employer authority” because it allows Medicaid enrollees (with the help of their designated representatives when appropriate) to decide who will be caring for them. All states with self-directed services programs provide employer authority to enrollees (Box 1). Additionally, all states allow individuals to hire independent providers (e.g., people who are not otherwise registered as Medicaid providers) for home care services.
Box 1. Example of Employer Authority
Helen is an 85-year-old women who lives alone and who has had a stroke. Following the stroke, she now requires assistance with activities of daily living. Helen’s state allows people to hire caregivers of their choosing, and under some conditions, family members. Helen elects to self-direct her care and chooses to hire her adult daughter, Emily, to be her caregiver. Due to her mother’s condition, Emily quits her job to care for her mom. Emily enrolls with the state and completes the required paperwork. The state is responsible for setting Emily’s hourly wage and number of authorized hours. The state approves 7 hours/day of paid caregiving. Helen determines that Emily will provide all 7 hours of care and assigns her tasks, abiding by the guidelines set by the state. Each week, Emily submits her time sheet to the state, who pays Emily and handles all withholding and taxes.
Among states that authorize self-direction, most states allow enrollees to establish payment rates for their caregivers (40) and to determine how much Medicaid funding is spent among the various authorized services (39) (Figure 3). Those abilities are referred to as “budget authority” because they give enrollees the power to decide how Medicaid funds are spent within an approved budget (Box 2).
Box 2. Example of Employer Authority and Budget Authority
Jason, a 32-year-old man, has a spinal cord injury and now requires a caregiver. Jason’s state allocated him a set budget per month to spend on caregiving and related expenses, but it’s up to Jason how to spend that money. Jason’s state contracts with a third party or organization (e.g., a “fiscal intermediary”) to help care recipients with required paperwork and to complete tasks such as tracking caregiver hours and paying caregivers. Through the fiscal intermediary, Jason develops a spending plan for his monthly allotment and hires a caregiver from a local home care organization that is registered with Medicaid. Jason and his hired caregiver, Steve, complete all paperwork required by the state’s approved fiscal intermediary. Since Jason’s program offers budget authority, Jason gets to decide the hourly wage and hours for Steve. After allocating money for Steve’s wages, Jason can use any extra allocated money to purchase additional approved supports that were included in his spending plan, such as meal delivery services on days that his caregiver does not work, and respite care, so his wife, who provides unpaid care outside of Steve’s hours, can have a break. Each month, Steve submits his hours to the fiscal intermediary. The fiscal intermediary is responsible for paying Steve and ensuring that Jason’s total spending stays within budget.
All states allowing self-direction provide financial management services to enrollees, and all but Mississippi and Nebraska use fiscal intermediaries to do so. When states offer budget authority, federal rules require them to provide participants with assistance in understanding billing and documentation requirements, performing payroll duties (which includes paying taxes and workers compensation), purchasing goods and services, and tracking expenditures to make sure spending is within the budget. Beyond that, care recipients often need help with finding caregivers and other services, and determining how to decide what services they need and in what amounts. A range of entities support beneficiaries in self-directing their care (see Figure 1, from the Medicaid and CHIP Payment and Access Commission). Nearly all states rely on outside organizations to help with the services, and all but Mississippi and Nebraska rely on fiscal intermediaries to handle tracking expenditures. In Mississippi, the state’s Department of Rehabilitation Services provides these functions and manages payroll for enrollees. In Nebraska, the state Medicaid agency serves as the employer/fiscal agent and directly handles financial management functions for individuals who self-direct. In many cases, Medicaid expenditures are paid directly to the fiscal intermediary or a state or local government unit assisting enrollees, and the third party pays providers.
While nearly all responding states allow Medicaid enrollees to self-direct their home care, the number of individuals doing so is unknown. KFF asked states, “What percentage of people are self-directing services under this waiver?” States could choose from five options: less than 25%, 25%–50%, 51%–75%, more than 75%, or unknown. Over half of states under each waiver type or state plan program did not report a percentage. Among programs that did respond, most reported that less than 25% of people are self-directing care.

How Many States Pay Family Caregivers and Through Which Home Care Programs?
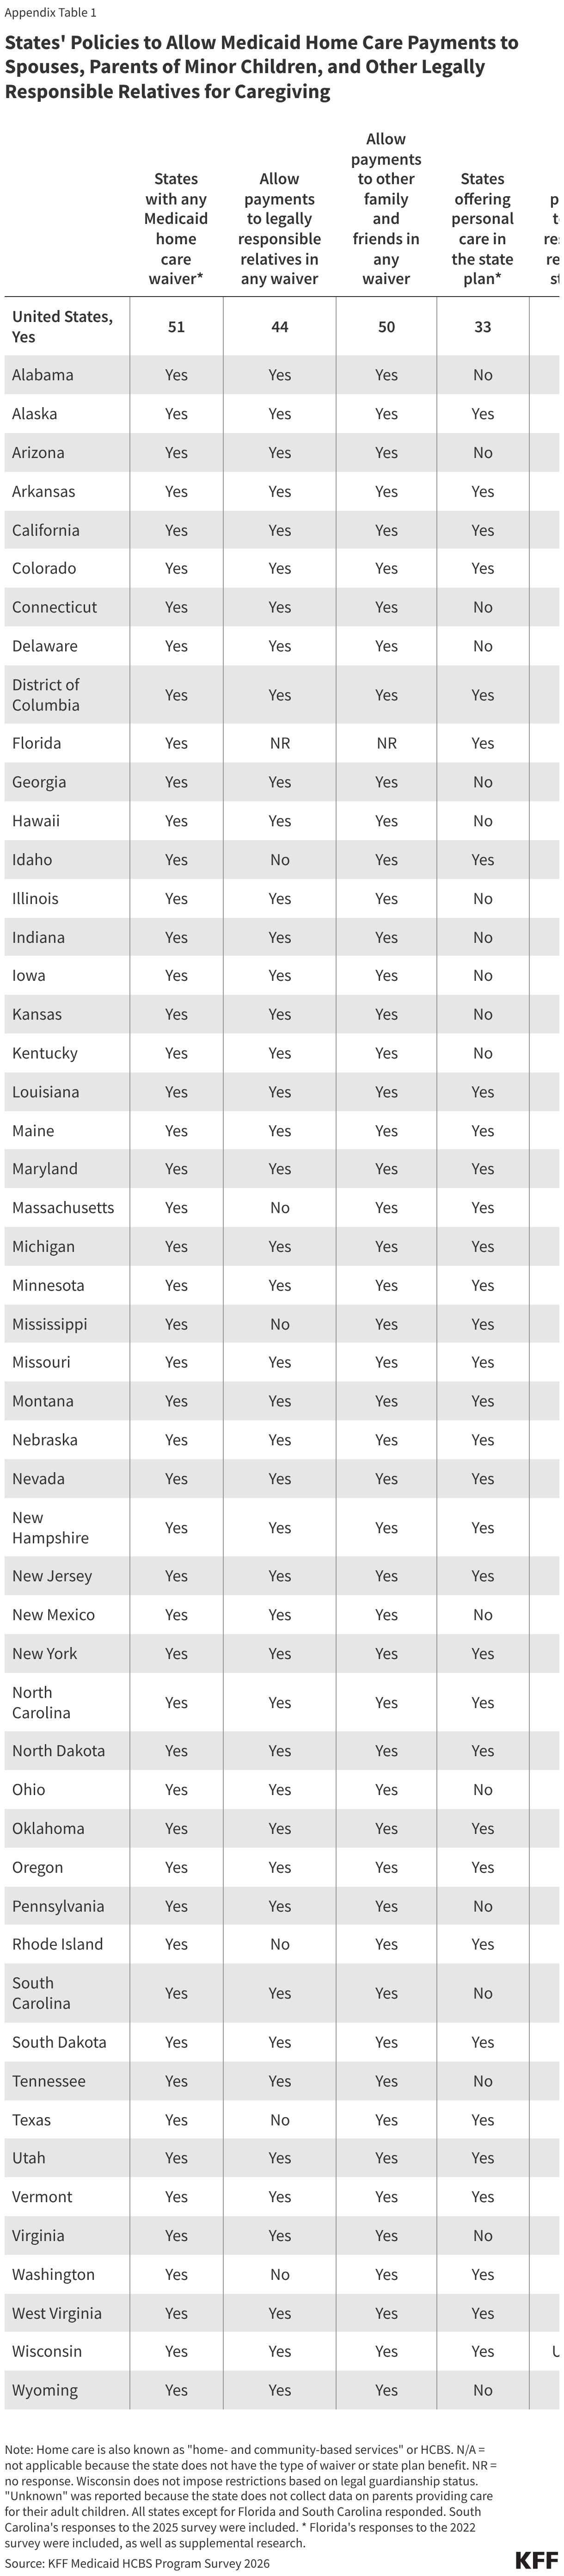
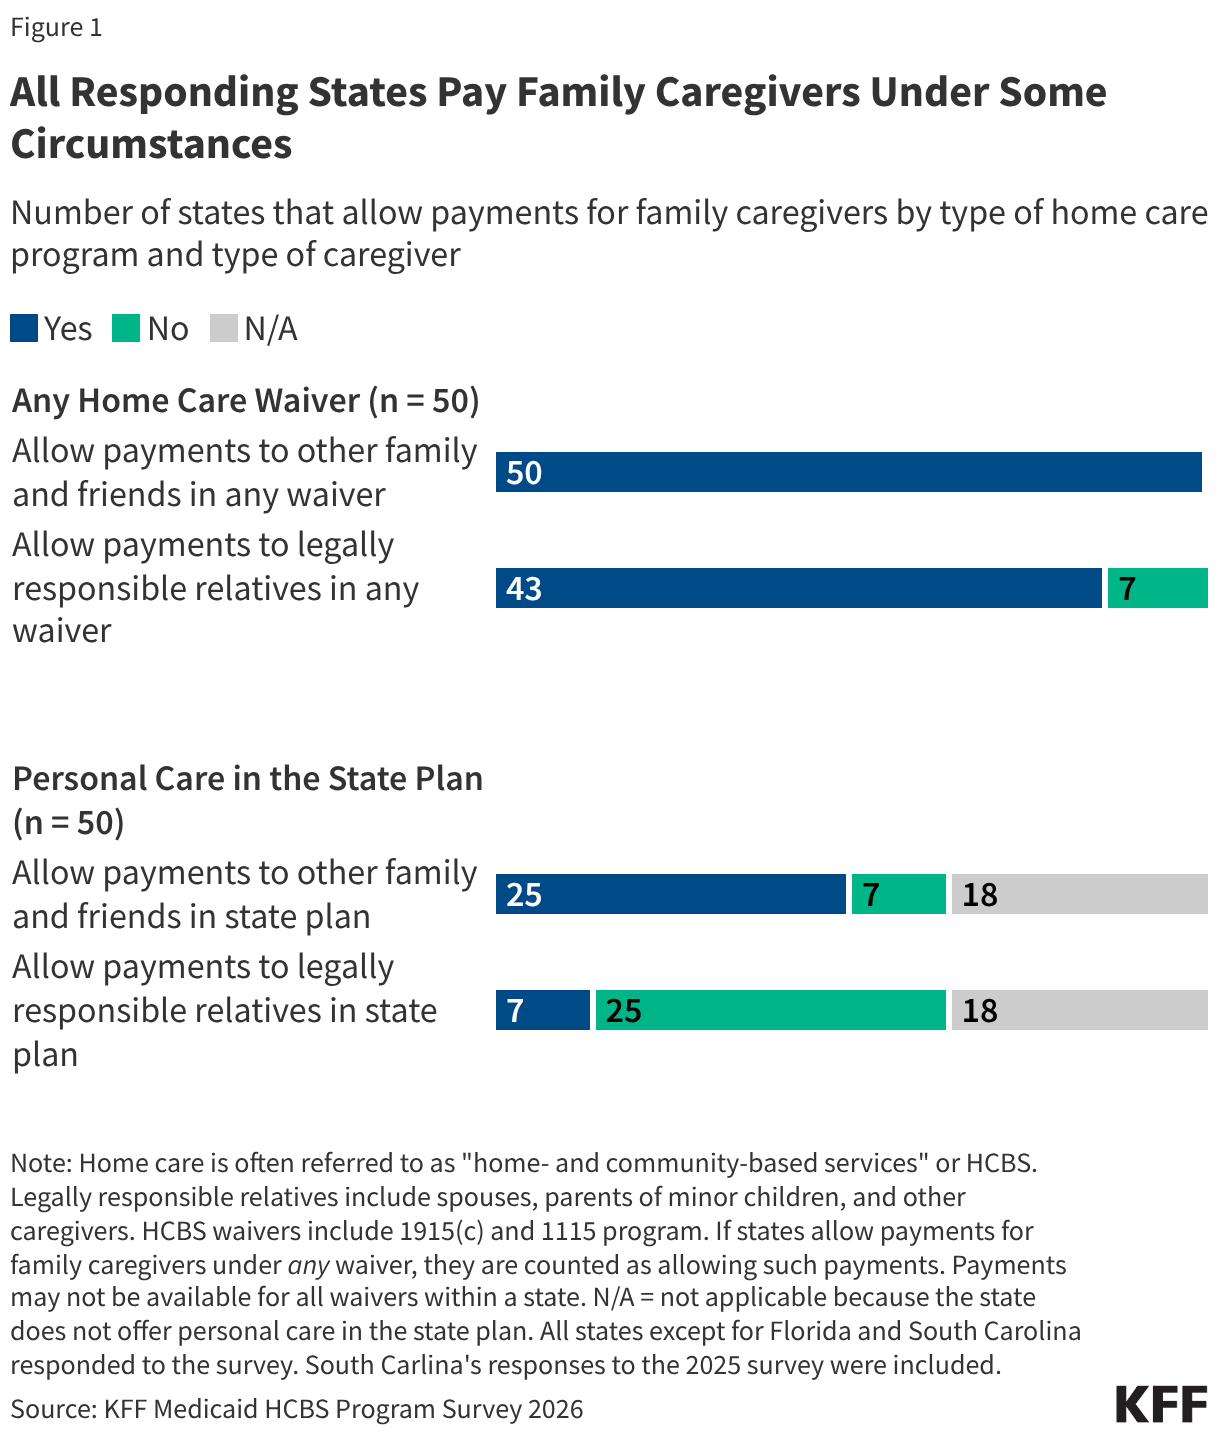
All responding states pay family caregivers through one or more Medicaid home care program (Figure 1, Appendix Table 1). Family caregivers can generally be paid to provide personal care, which may be offered through several different types of Medicaid home care programs. Personal care may be provided through waivers such as the 1115 or 1915(c) programs, through the Medicaid state plan, or through a combination of both. Waiver services tend to encompass a wider range of benefits than the state plan benefit, but waivers are usually restricted to specific groups of Medicaid enrollees based on geographic region, income, or type of disability, and are often available only to a limited number of people, resulting in waiting lists.
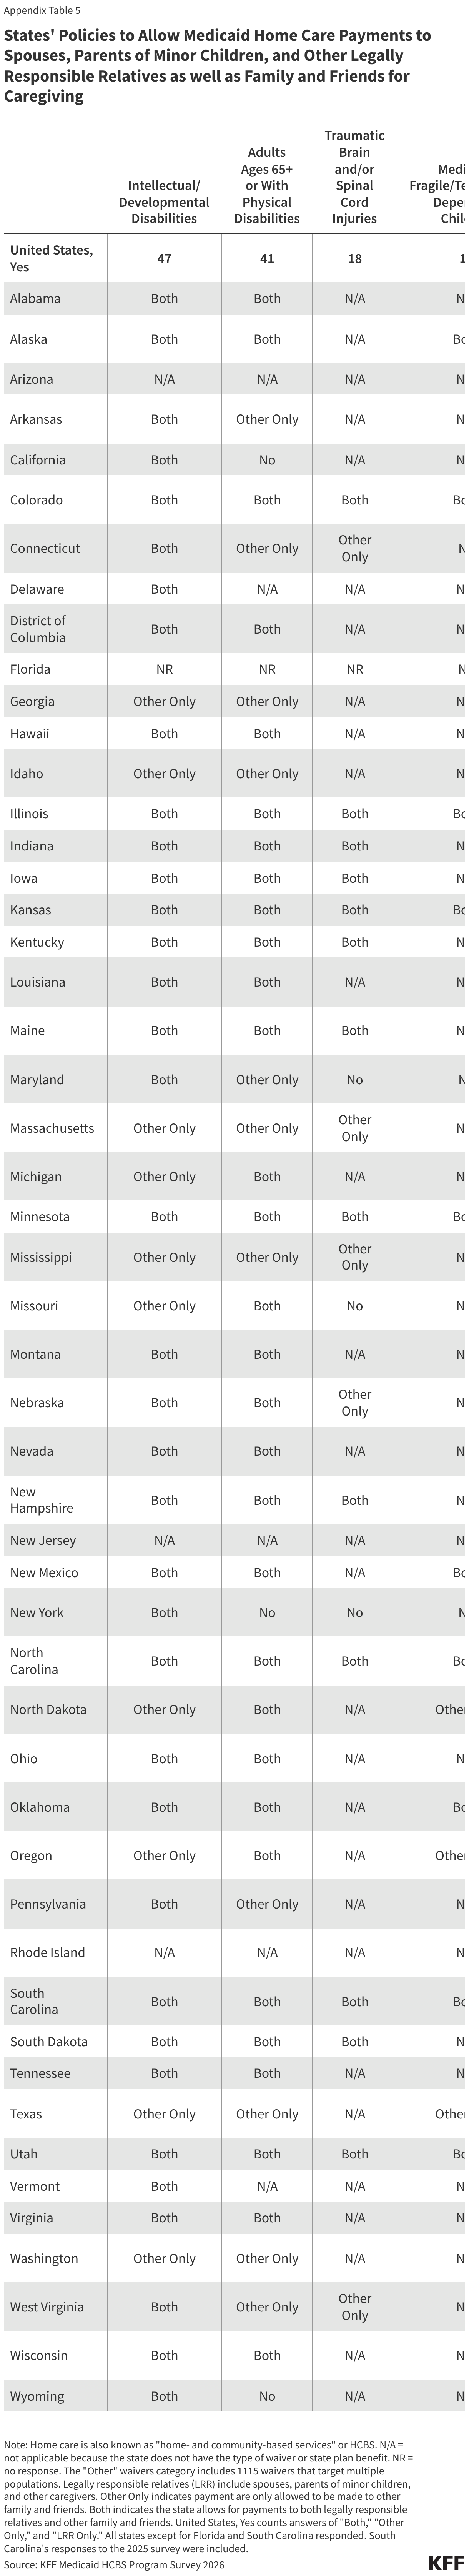
All responding states allow payments to family and friends through one or more waiver programs, but fewer states allow payments to legally responsible relatives. Forty-four states allow payments to legally responsible relatives through waiver programs. Payments to legally responsible relatives are less common than those to other family and friends because of additional legal requirements that apply to those payments (Box 3). In 2026, Nebraska started newly permitting payments to legally responsible relatives in its waivers for people with I/DD and for adults ages 65 and older and people with physical disabilities.
Payments to family caregivers are less common through the state plan—allowed by 25 states for other family and friends and by 7 states for legally responsible relatives. States pay family caregivers through the state plan less frequently because fewer states offer personal care through the state plan and because the legal requirements governing state plan services are more restrictive than those governing waiver services. One state, Nebraska, newly started allowing payments to legally responsible adults through the state plan in 2026.
Box 3: What Are the Legal Requirements for Paying Family Caregivers?
Medicaid laws have more complicated requirements for states to pay legally responsible relatives than is the case for other types of family and friend caregivers. The specific legal requirements for paying family caregivers are complicated and differ across home care programs:
• For personal care offered through the state plan using section 1905 authority, there is a federal prohibition on paying for services provided by spouses and parents of minor children (who make up most, but not all, legally responsible relatives). Other family and friends may be paid if they meet applicable provider qualifications, there are strict controls on the payments, and the provision of care is justified (which can be done when there is a lack of other qualified providers in the area).
• For home care offered through waiver programs, the requirements governing payments to family and friends are similar to those governing personal care through section 1905 authority. A key difference is that states may pay legally responsible relatives when the services being provided are “extraordinary care,” which is defined as care that exceeds the range of activities a legally responsible relative would ordinarily perform and is necessary to ensure health and welfare and to avoid institutionalization.
• For personal care offered through the state plan under sections 1915(i), (j), or (k), states may pay legally responsible relatives using criteria similar to those of the waiver programs. However, some of those authorities designate a family member to be the recipient’s legal representative and may prohibit payments to legal representatives.
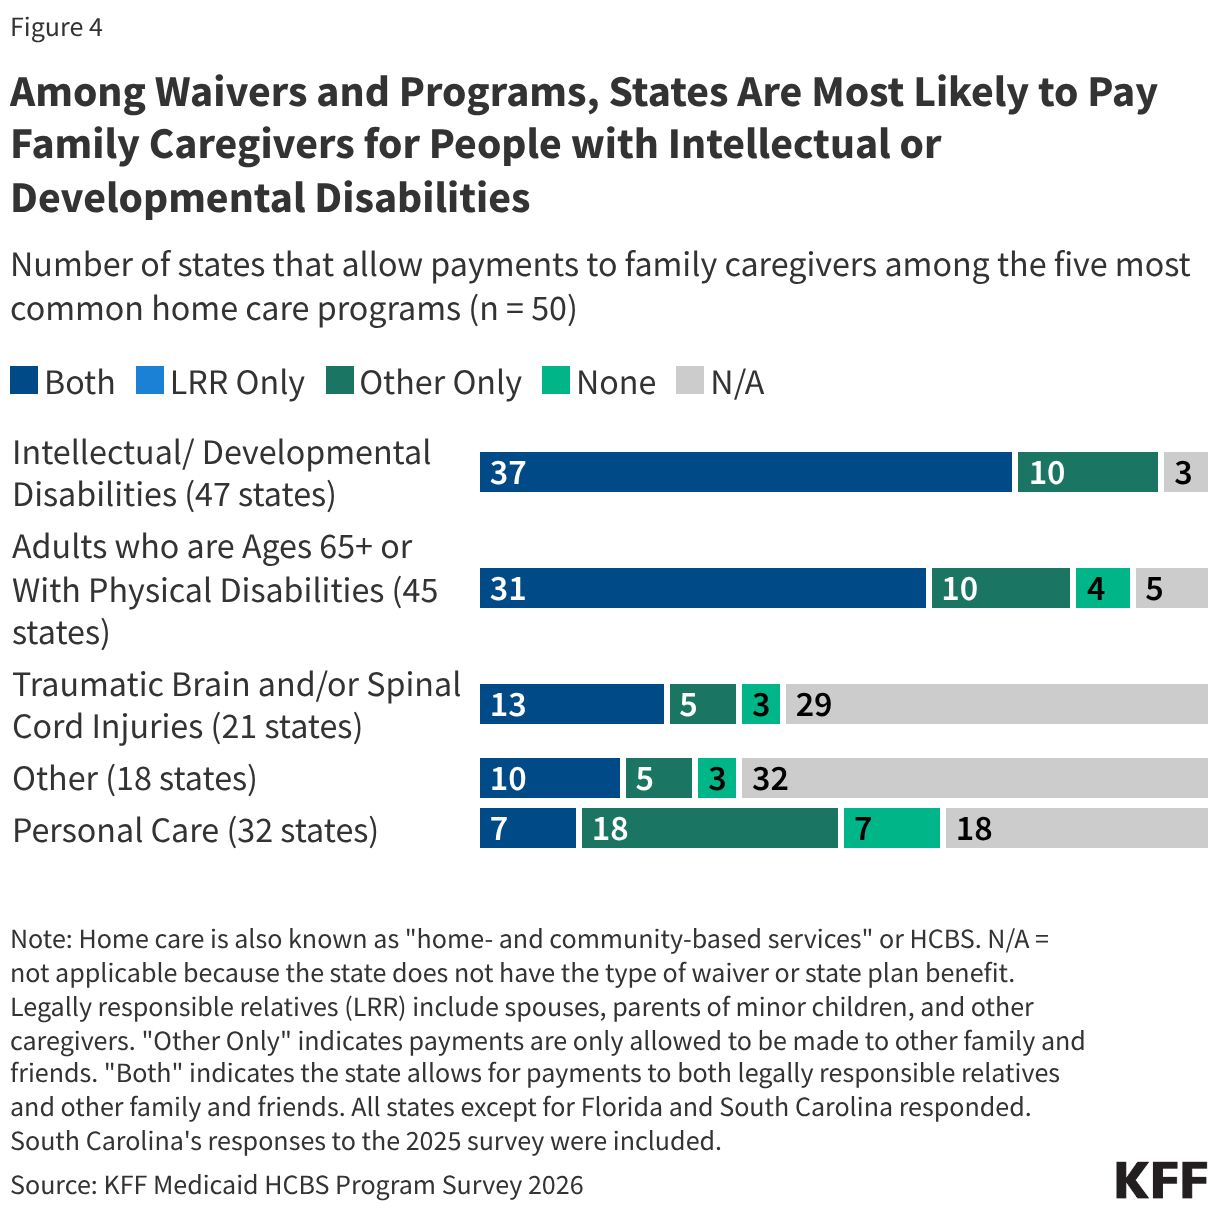
Payments for family caregivers are most common under waivers for people with I/DD (Figure 4, Appendix Table 5). Among the 47 states that responded to the survey and have waivers for people with I/DD, all 47 allow payments to family caregivers. There are fewer states with other types of waivers, and not all the other waivers allow payments to family caregivers. Among the 45 responding states with waivers for adults ages 65 and older and those with physical disabilities, 41 pay family caregivers, and among the 21 states with waivers for people with traumatic brain and/or spinal cord injuries, 18 do.
While all responding states allow payments to family caregivers, it is unknown what percentage of waiver participants are receiving paid care from family caregivers. KFF asked states, “What percentage of waiver recipients are receiving paid care from their legally responsible relatives/family members who are not legally responsible relatives?” Over half of states did not report the percentage of waiver recipients receiving paid care from either legally responsible relatives or other family members or friends. It is also unknown how often people with paid family caregivers also receive other paid care.
While most states allow family members to be paid caregivers, states do not collect much information about those caregivers. KFF asked states whether they track information on family caregivers’ name, age, income, and Medicaid eligibility. Just over half of states collected information about family caregivers, with most of the data collected focused on paid caregivers’ names and ages. Very few states collected any information on unpaid caregivers. Only 14 states reported knowing how many paid and/or unpaid caregivers were providing services to waiver participants and even fewer (7 states) knew if family caregivers were enrolled in Medicaid through the Affordable Care Act (ACA) expansion. Starting January 1, 2027, people who are eligible for Medicaid through the ACA expansion will be required to meet new community engagement requirements. Caring for a family member with a disability can count towards the work requirement minimum hours or qualify caregivers for an exemption from the requirement. However, the lack of data on caregivers’ Medicaid eligibility will likely increase the paperwork burden on family caregivers who are subject to work requirements because they will be required to provide documentation showing they are meeting the requirements or qualify for an exemption.
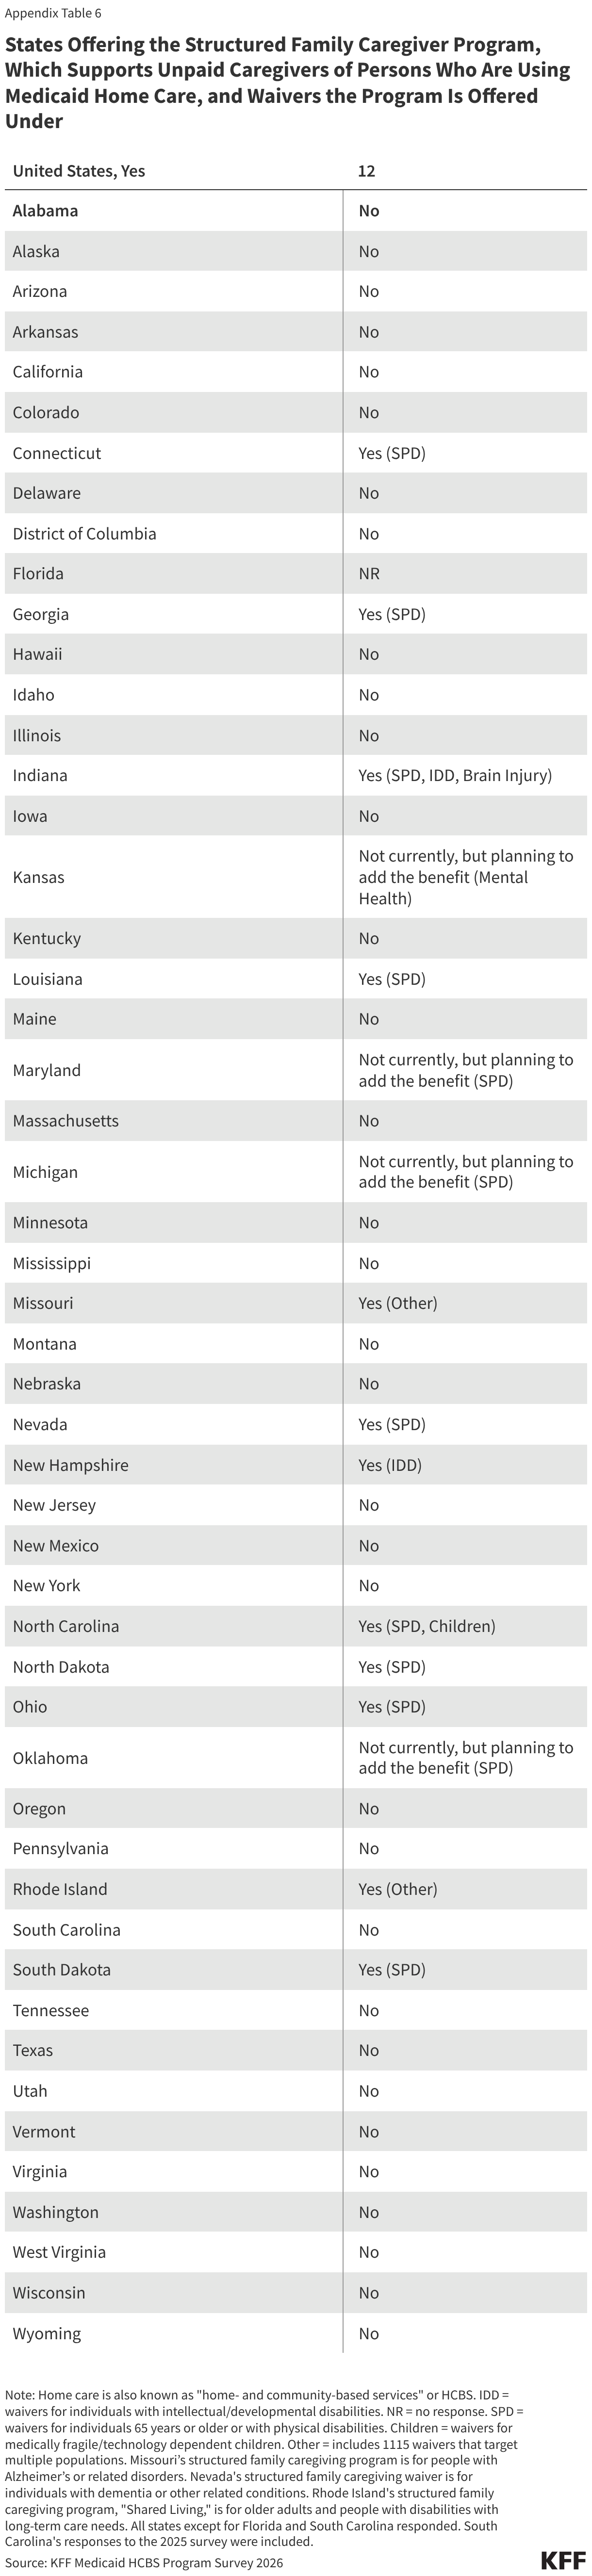
In most cases, family caregivers receive hourly wages like those of other employees, but 12 states have adopted programs known as structured family caregiving, in which family members are paid a per diem rate (Appendix Table 6). Structured family caregiving is a Medicaid benefit that supports unpaid caregivers of people who use Medicaid home care through waiver programs. In the structured program, Medicaid pays provider agencies a daily stipend for participants. The agency is responsible for directing a care coordinator or social worker and a nurse to oversee the family caregiver, answer health-related questions, and provide emotional support; conducting home visits about once per month; and passing a fixed percentage of the stipend (usually 50%–65%) on to the family caregiver. Among the handful of payment rates reported in an overview of the program by the American Council on Aging, payments to family members in 2026 are about $40–$70 per day. States reported structured family caregiving programs in the following home care waivers:
- Adults ages 65 and older and those with physical disabilities in nine states (Connecticut, Georgia, Indiana, Louisiana, North Carolina, North Dakota, Ohio, Rhode Island, and South Dakota),
- People with I/DD in Indiana and New Hampshire,
- Medically fragile children in North Carolina,
- People with traumatic brain and/or spinal cord injuries in Indiana, and
- People with Alzheimer’s or dementia and related disorders in Missouri and Nevada.
Nevada’s structured family caregiving program is new in 2026, but it represents a new service rather than replacing a program that pays providers on an hourly basis. The program is available under a new waiver that was approved in 2025 but did not launch until 2026, which the state attributed to shortages among case management providers.
Four additional states do not currently offer structured family caregiving but plan to add the benefit (Kansas for individuals with mental health conditions, and Maryland, Michigan, and Oklahoma for adults ages 65 and older and those with physical disabilities). Right now, those waivers in Kansas and Maryland do not offer any payments to family caregivers, so the structured family caregiving benefit will allow families to newly receive some compensation. One state (Massachusetts) offers structured family caregiving as a state plan benefit for adults in foster care.
What Other Types of Support Does Medicaid Home Care Provide for Family Caregivers?
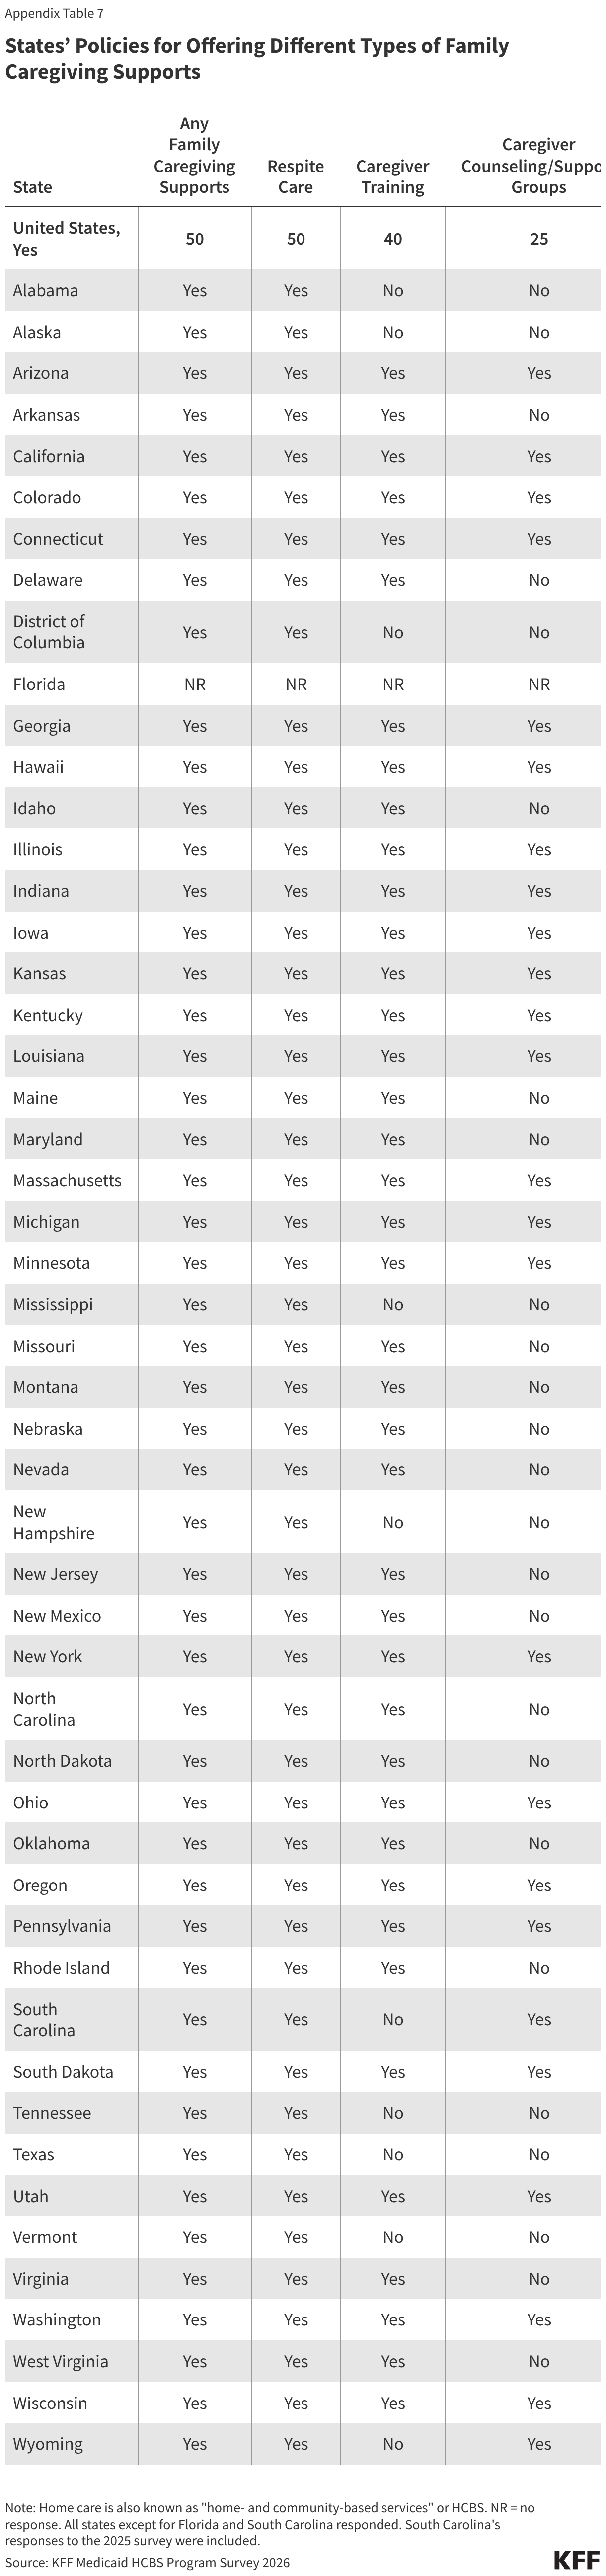
All responding states provide support for family caregivers—who may be paid or unpaid—and most offer more than one type of support (Figure 5, Appendix Table 7). All responding states reported covering respite care, which provides short-term relief for caregivers, allowing them to rest, travel, attend appointments, or spend time with other family and friends. Other commonly covered benefits include caregiver training (40 states) and counseling or support groups (25 states). Delaware, Missouri, Nevada, and Rhode Island reported newly covering caregiver training in 2026; and Arizona is implementing a new program offering peer-to-peer family support for paid and unpaid family caregivers.
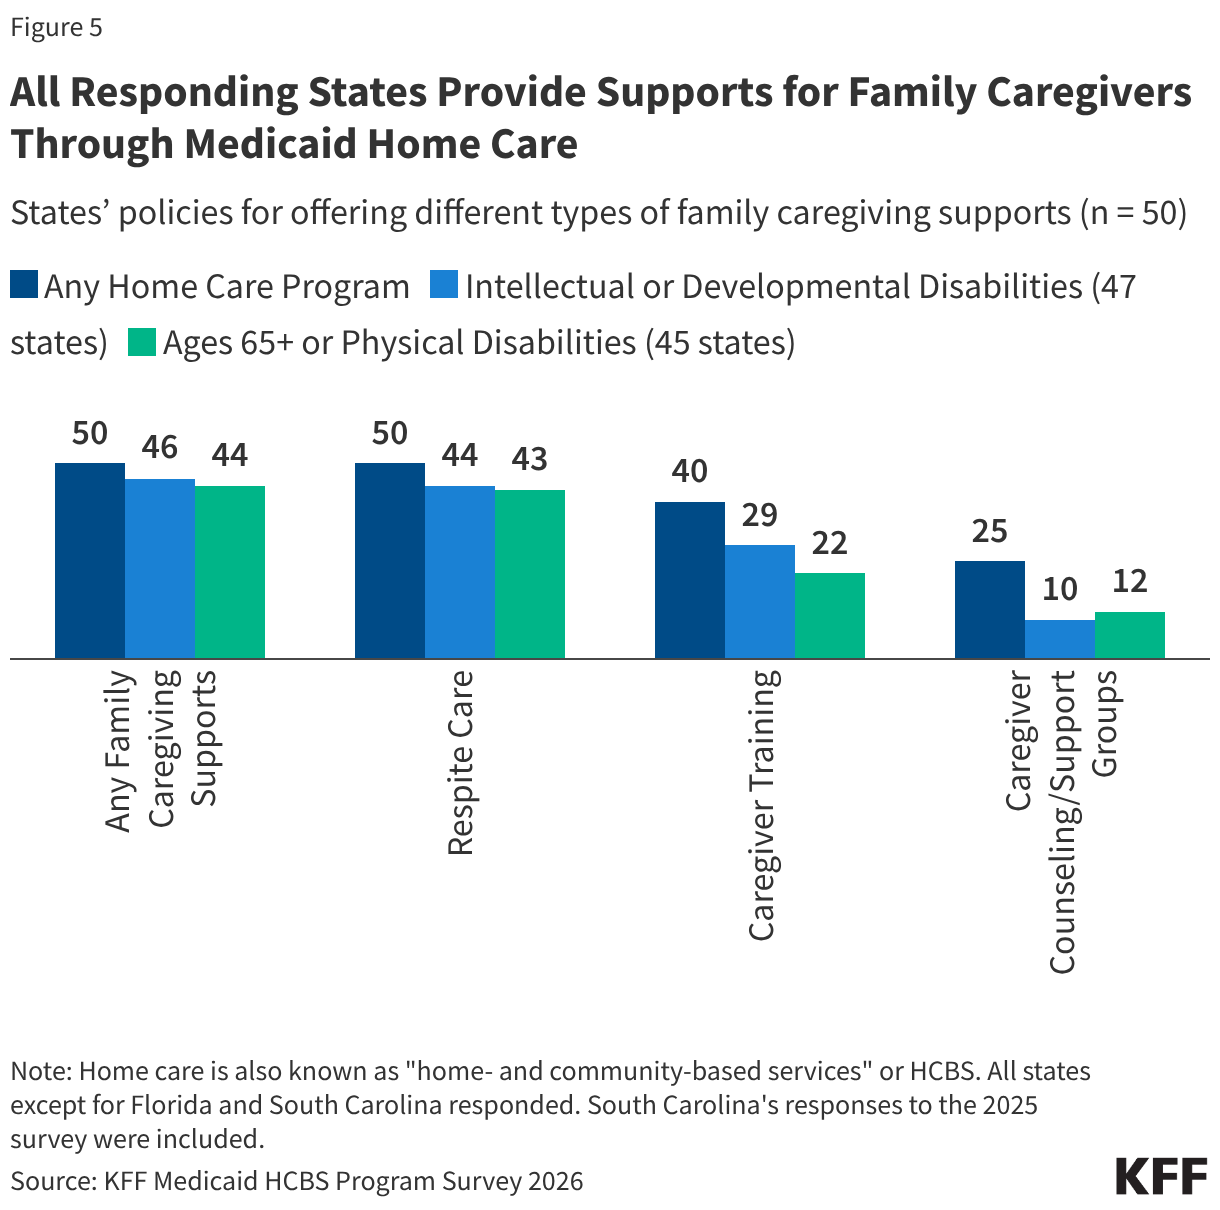
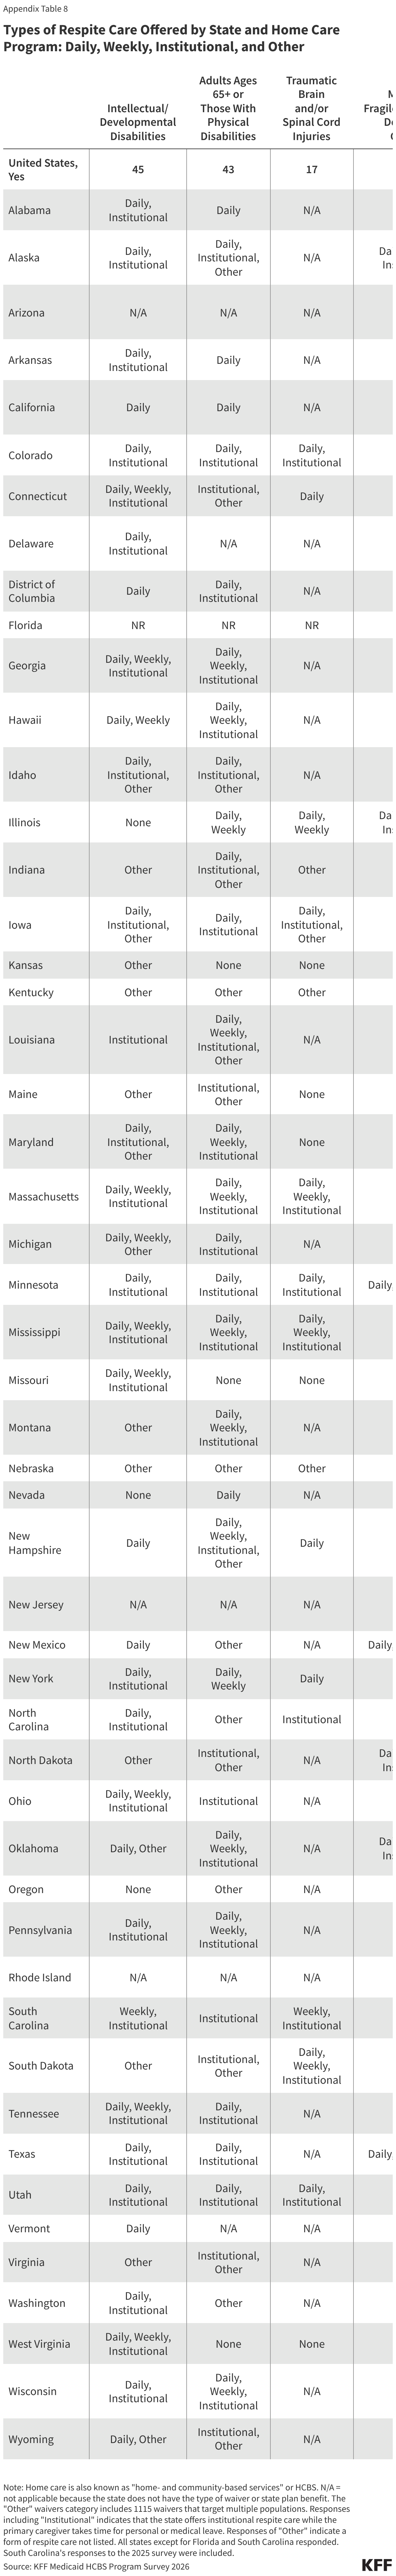
Respite care may be provided anywhere from a few hours to several weeks at a time. Medicare covers respite care only for people who are receiving hospice care, which is available only to people who are terminally ill and elect to receive comfort care instead of curative care for their illness. That makes Medicaid’s respite care the primary source of coverage for caregivers of people with Medicare and Medicaid. Respite care is offered most frequently under waivers for people with I/DD (44 states) and adults ages 65 and older and those with disabilities (43 states).
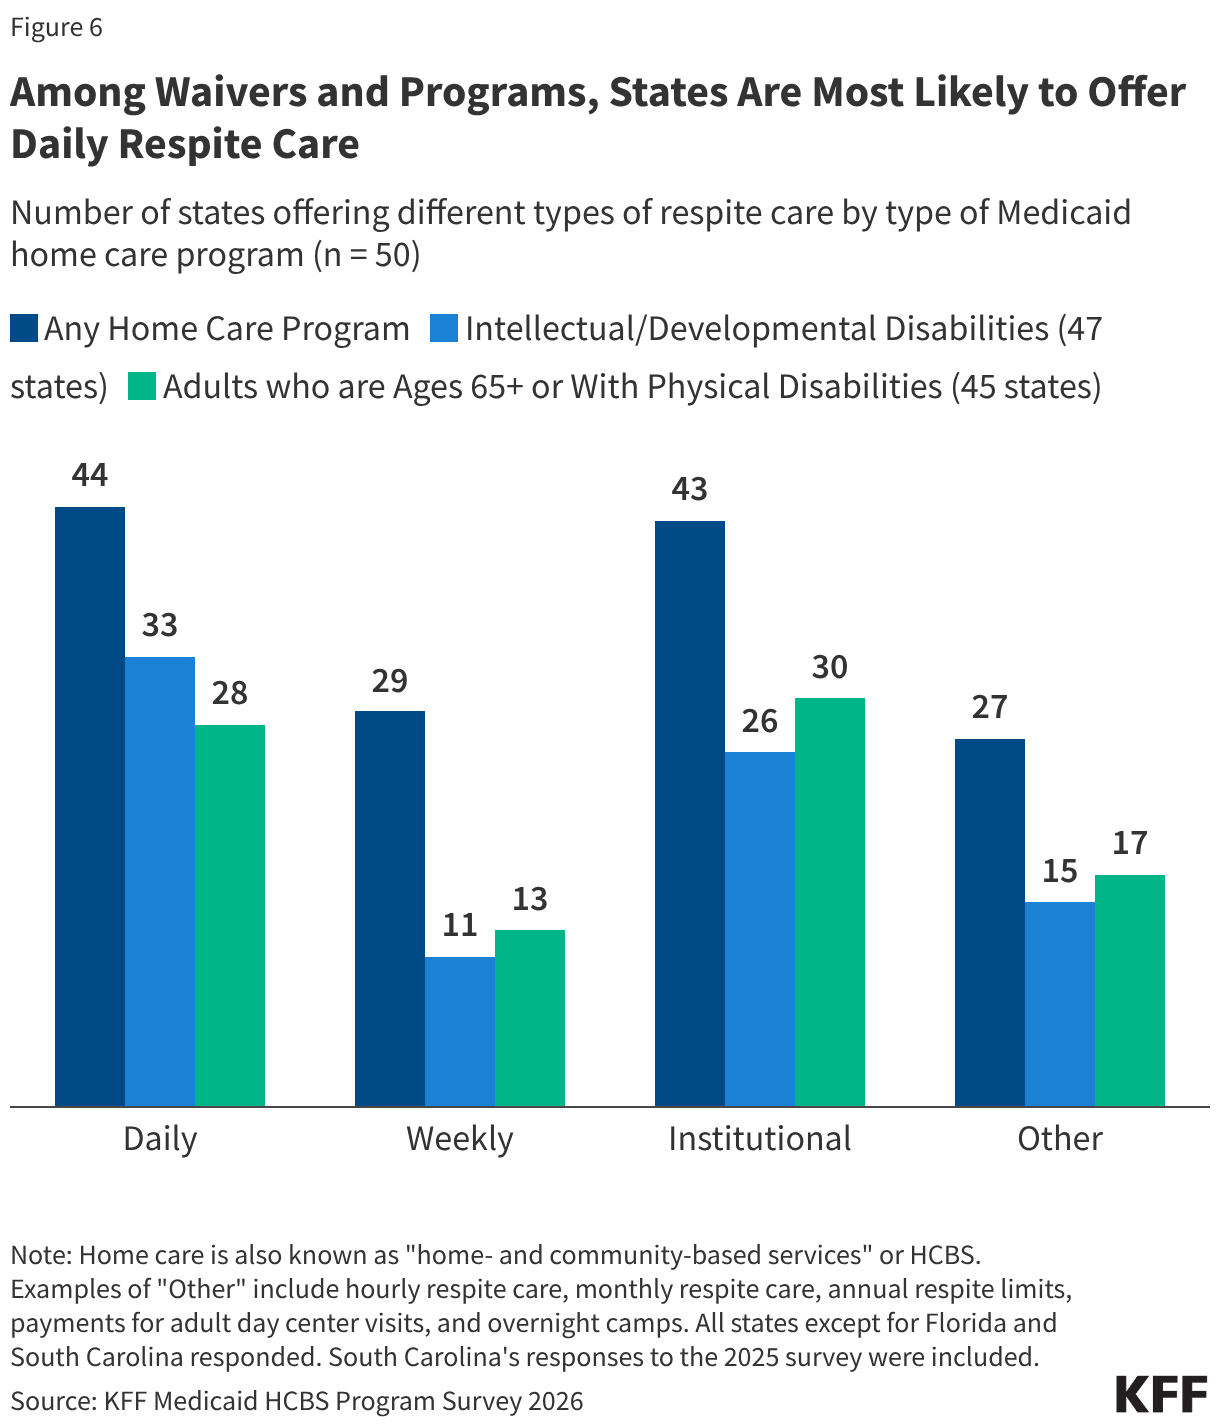
Daily respite care is offered by most states (44 states), followed by institutional respite care (43 states) (Figure 6, Appendix Table 8). Daily respite care is available under waivers for people with I/DD in 33 states and available in 28 states within waivers for adults ages 65 and older and those with physical disabilities. Thirty states provide institutional respite care within waivers for adults ages 65 and older and those with physical disabilities, and 26 provide it within waivers for people with I/DD. Weekly respite care is the least frequently offered (29 states total), and over half of states (27) report offering other types of respite care, such as hourly, monthly, or annual.
This work was supported in part by Arnold Ventures. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.
Appendix Tables