
A Closer Look at State Directed Payments for Nursing Home Services
The 2025 reconciliation law included major eligibility and financing changes to Medicaid, and at the time of enactment, the Congressional Budget Office (CBO) estimated a reduction in federal Medicaid spending of $911 billion from 2025 through 2034. Some of the reductions stem from new restrictions on Medicaid state directed payments (SDPs) for hospital, nursing home, and other health care services. While states are generally prohibited from directing how managed care organizations (MCOs) pay for care, states can implement SDPs that require MCOs to increase rates or set minimum rates for specified Medicaid services. In authorizing SDPs, the Centers for Medicare and Medicaid Services (CMS) aimed to help states improve access to care and provider participation. Many states that contract with MCOs use SDPs to make uniform rate increases that function like supplemental payments in fee-for-service (FFS) Medicaid. Building on previous analysis of SDPs, this issue brief takes a closer look at SDPs for nursing home services.
The analysis includes 20 preprints from 15 states, from SDPs that were publicly available and approved from January 1, 2024 through May 12, 2026. Preprints are application forms submitted to the federal government that document how states direct Medicaid managed care plans to pay providers using SDPs. Preprints are the only national source of data on SDPs but are limited because there are gaps in data provided by the preprints (see Methods for more details). Other preprints for nursing home services may have been approved since May 12, 2026. Key takeaways include:
- Annual spending on SDPs for nursing home services is estimated at $3.7 billion in total spending and $2.2 billion in federal spending, which is about three percent of total SDP spending and two percent of total federal SDP spending.
- At least 15 states have SDPs that pay for nursing home services, and many of those payments could be reduced under new limits for SDPs from the 2025 reconciliation law.
- Much remains unknown about how forthcoming policy changes for SDPs will affect states, nursing homes, and nursing home residents (two-thirds of whom have Medicaid as a primary payer), but data about existing SDPs highlight states and services for which changes could be most substantial.
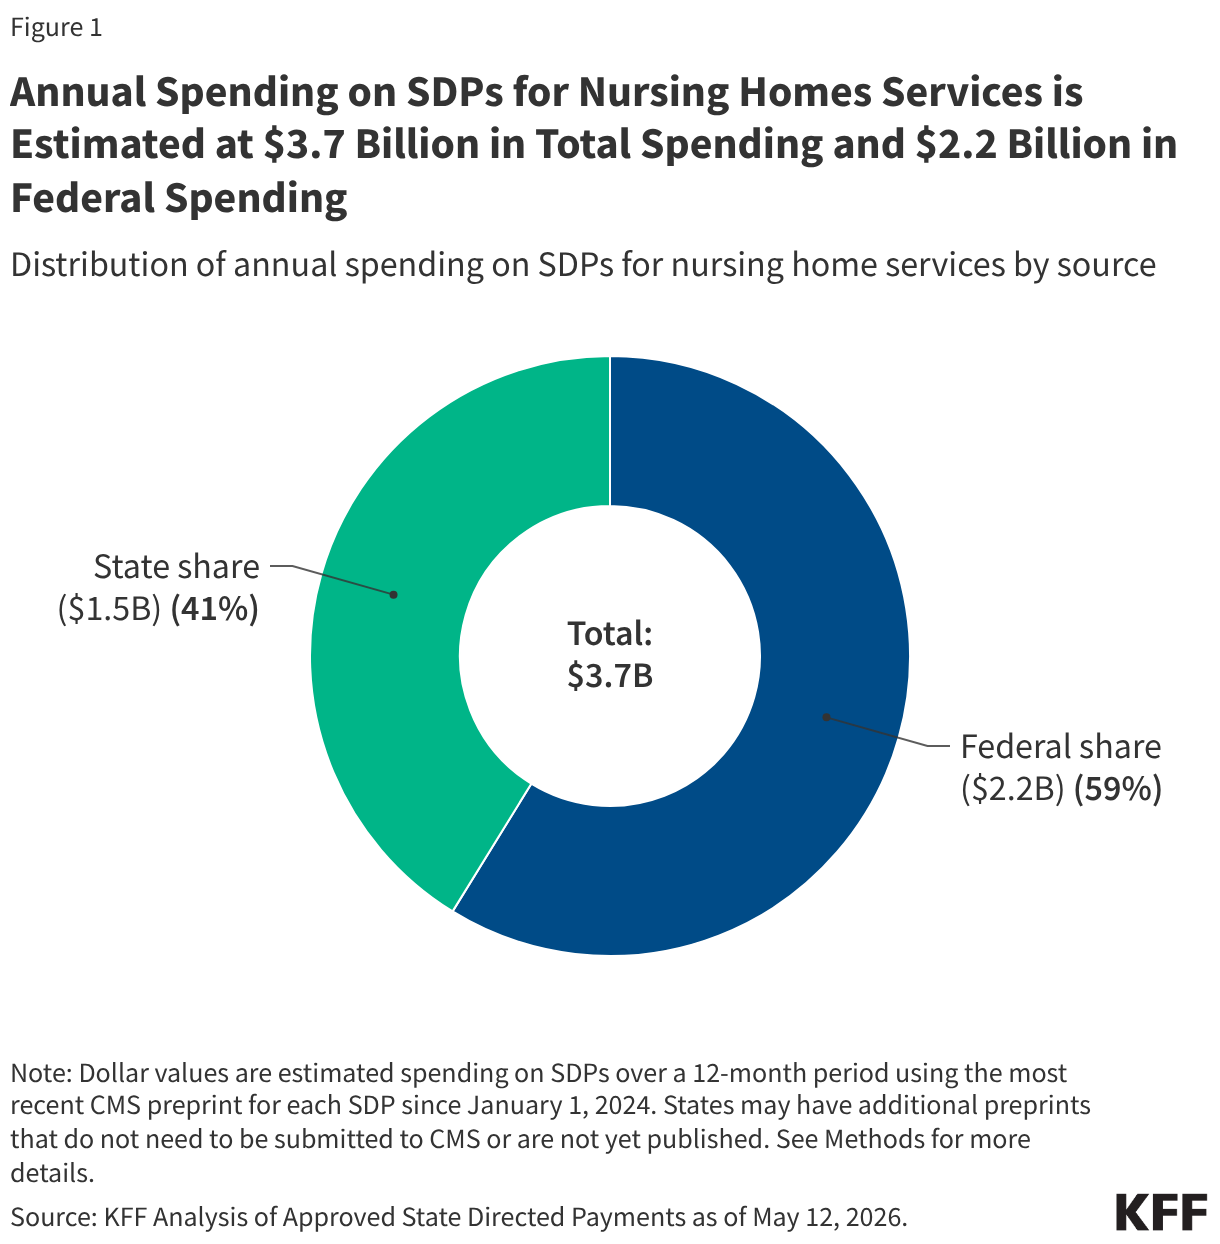
Annual spending on state directed payments (SDPs) for nursing home services is estimated at $3.7 billion in total spending and $2.2 billion in federal spending (Figure 1). This is only about 2% of total federal SDP spending, with most (84%) federal SDP spending directed to hospital services. Based on states’ projected spending in the preprints, the federal government pays an estimated 60% of total spending on SDPs for nursing home services, and the remainder is paid through the state share of SDP financing. The federal and state shares of financing are determined using the standard formulas for Medicaid financing and reflect the state’s federal matching assistance percentage. The state share of financing may come from a variety of sources including state general fund revenues, provider taxes, and intergovernmental transfers. Among the 15 states with SDPs for nursing home services, 11 finance part or all of the state share with provider taxes and 4 states finance part or all of the state share with Intergovernmental transfers.
Federal spending on SDPs for nursing home services ($2.2 billion) accounts for 2.4% of total federal spending on SDPs. Federal spending on SDPs is expected to decrease in future years because of new limits established by the 2025 reconciliation law. Under the limits, the total payment amount under the SDP may not exceed 100% of the Medicare payment rate in states that have adopted the Affordable Care Act (ACA) Medicaid expansion (“expansion states”) and 110% of the Medicare payment rate for non-expansion states. Payment rates for services without an applicable Medicare payment rate are limited to Medicaid fee-for-service rates. Certain SDPs are initially grandfathered (i.e., allowed to continue), but total spending amounts will be reduced by 10 percentage points each year (starting January 1, 2028) until they reach the allowable Medicare-related payment limit.
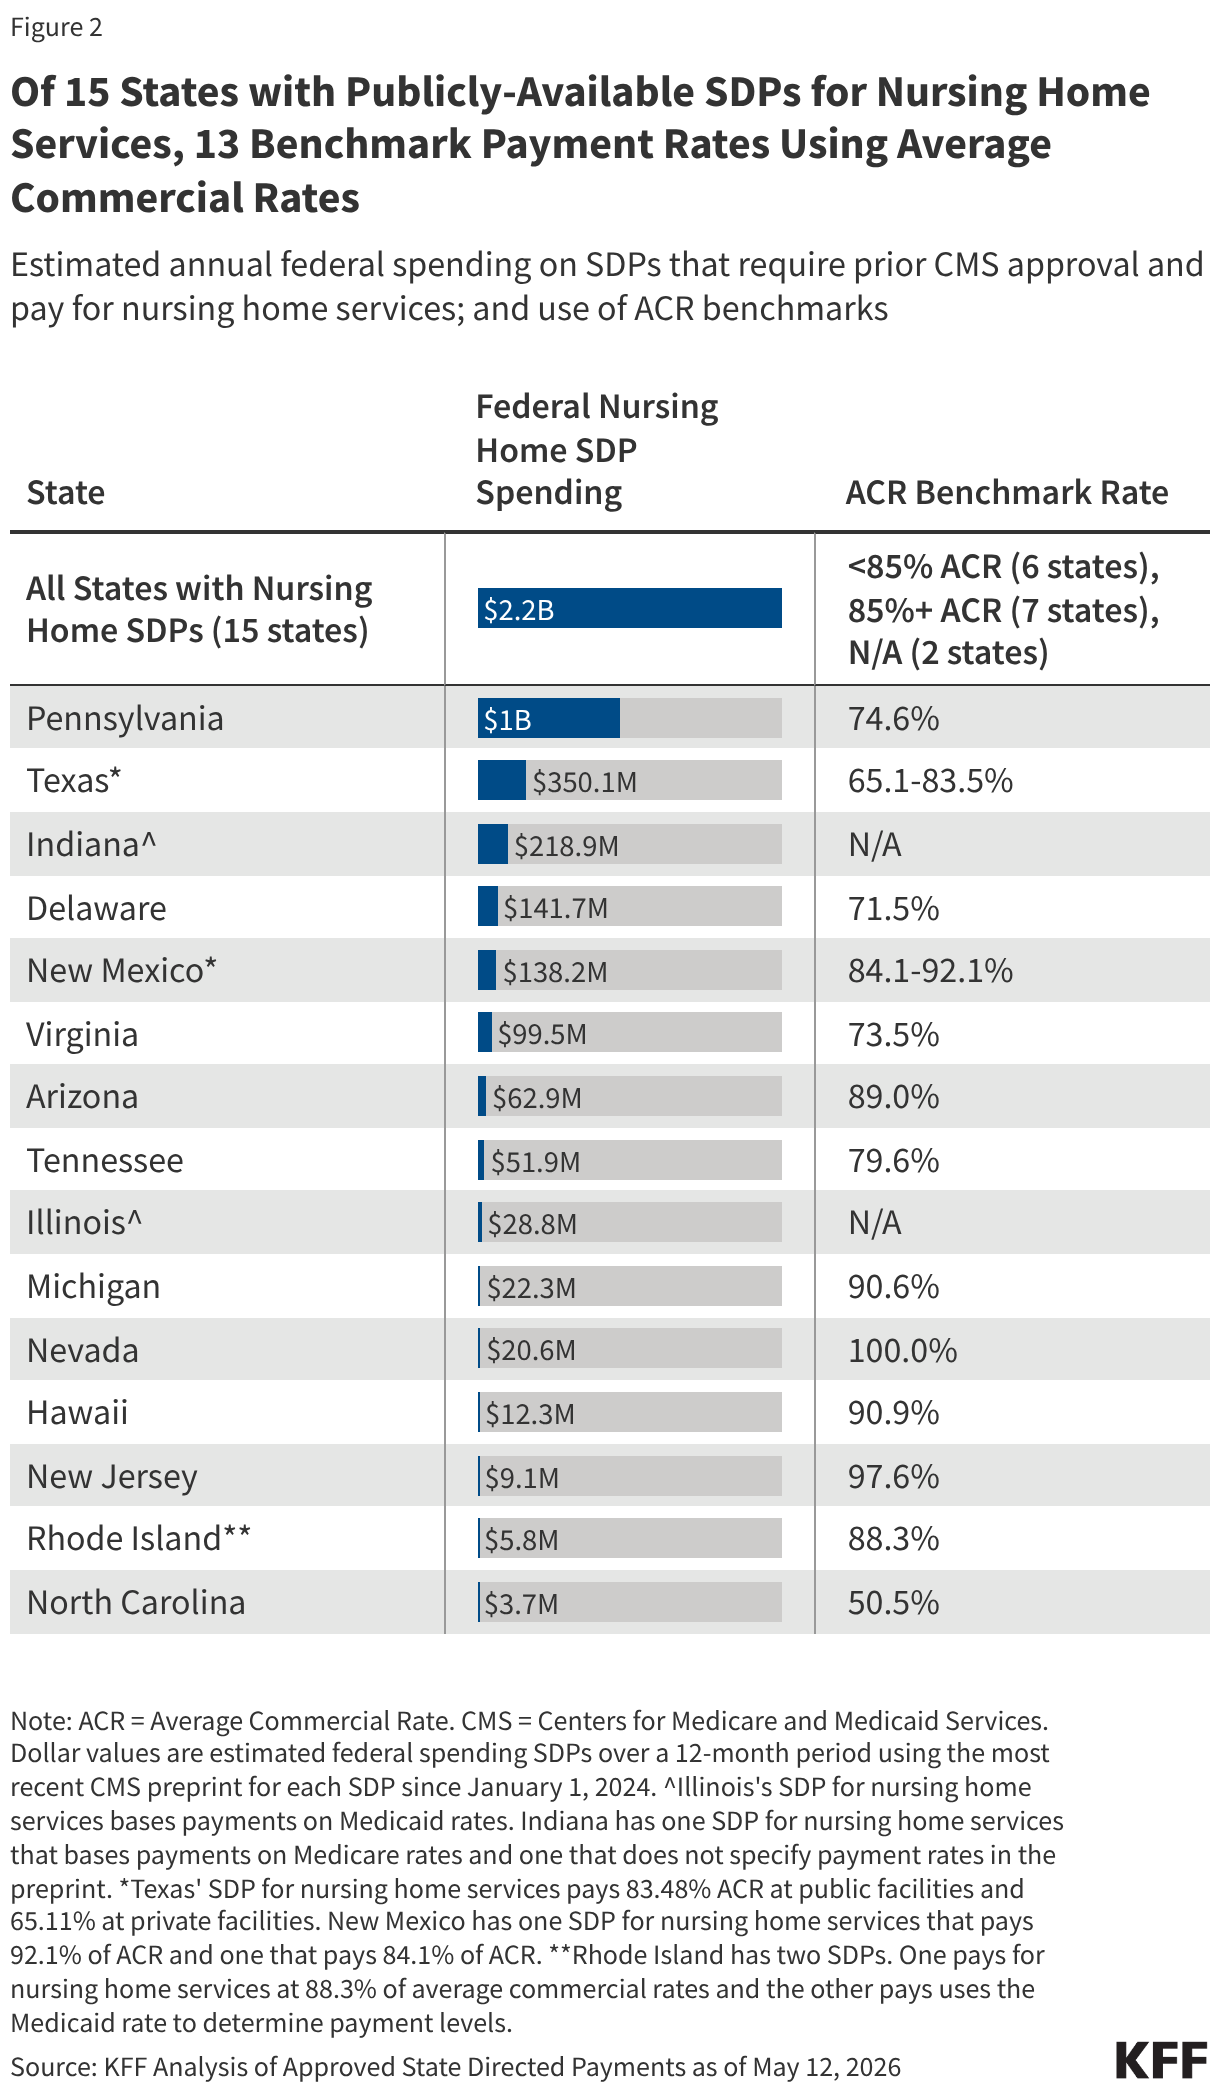
Of the 15 states with publicly available SDPs for nursing home services, 13 benchmark payment rates using average commercial rates (Figure 2). Among these 13 states, 12 states exclusively use average commercial rates when establishing SDP payment rates for nursing home services. Pennsylvania accounts for nearly half (47%) of the $2.2 billion in federal spending on SDPs for nursing home services and sets payment rates at 74.6% of average commercial rates. Rhode Island has two SDPs for nursing home services: One pays for nursing home services at 88.3% of average commercial rates, and the other uses the Medicaid rate to determine payment levels. Indiana and Illinois do not use the average commercial rate to benchmark any of their SDPs for nursing home services. Illinois benchmarks its SDP for nursing home services to Medicaid rates. Indiana benchmarks one SDP for nursing home services to Medicare and does not specify a benchmark in the other SDP.
It is unclear how much payment rates will have to decrease to come into compliance with the new payment limits established in the 2025 reconciliation law. For other types of services, research shows that average commercial rates are higher than Medicare rates, particularly in the case of hospital services and physician services. However, there are not similar data or studies available to estimate how average commercial rates for nursing homes compare with Medicare or Medicaid rates, making it more difficult to anticipate how the changes in law could affect nursing home payment rates nationally. States may have additional data internally, but those are not publicly available, and variation across states could be considerable.
In its regulatory analysis of the proposed regulation on SDPs, CMS assumed that Medicaid payment rates were 80% of Medicare rates for nursing home services and that average commercial rates were 150% of Medicare rates, but also highlighted uncertainty. CMS writes that “there is little information on nursing [home] prices and the services that Medicare covers may be significantly different than those covered by private payers and Medicaid.” CMS’s finding is consistent with data from a 2023 Medicaid and CHIP Payment and Access Commission (MACPAC) analysis of Medicaid nursing home payment rates relative to Medicare payment rates and costs. The analysis found that Medicaid base payment rates (not accounting for supplemental payments) varied considerably but were generally lower than those of Medicare. However, MACPAC reported that Medicaid and Medicare rates were not comparable because of differences in residents’ level of need. The proposed regulation specifies that the skilled nursing facility prospective payment system will define Medicare payment rates for nursing facility services, but it is unclear how that per diem payment rate will translate into the limits on SDPs for nursing home services.
Nursing homes will likely vary in how they are impacted by lower SDP spending, and it is unknown how the new limits will affect access to care among Medicaid enrollees who use nursing home services. The effects for specific nursing homes will depend on how much they are currently receiving in SDPs, how much their revenues decline as the new limits take effect, and how dependent they are on SDP revenues. Effects will vary across states but also within states because states may direct SDPs to a subset of nursing homes, or sometimes a single nursing home, and among eligible nursing homes, SDPs vary with Medicaid patient volume. Nursing homes’ abilities to absorb reduced payment rates also varies. For nursing homes with relatively high operating margins, changes to SDP revenues might be more easily absorbed. On the other hand, nursing homes with relatively low operating margins may adapt in ways that affect Medicaid enrollees’ access to care, such as reducing the number of Medicaid beds available or closing.
This work was supported in part by Arnold Ventures and The John A. Hartford Foundation. KFF maintains full editorial control over all of its policy analysis, polling, and journalism activities.
Methods
Data source: This analysis uses data available from the list of approved state directed payment preprints published by the Centers for Medicare and Medicaid Services (CMS) as of May 12, 2026. The approved state directed payment (SDP) preprints are PDF versions of forms that are completed by states and approved by CMS. States are required to seek approval using such a preprint for any SDP that requires managed care organizations (MCOs) to pay for services at any rate other than fee-for-service (FFS) Medicare or Medicaid rates. The approved preprints are often posted online 6–12 months after their start date, although some approved preprints are posted online much later.
KFF developed a Python script to download the available PDFs, extract relevant data from them, and standardize certain fields. Each preprint was turned into one row in a spreadsheet. Data from tables within the preprint were extracted and converted into separate tables in KFF’s data file with each row in the preprint table converted into a row in the spreadsheet table.
SDP preprint inclusion criteria: KFF included all SDPs in the analysis with a rating period start date of January 1, 2024 onwards for the 50 states and Washington DC (hereafter referred to as a state). Puerto Rico was the only territory that had published SDPs, which were excluded. In each case, KFF only kept the most recent preprint for any given SDP. For example, if an SDP had an initial approval in 2024 and then renewals in 2025 and 2026, KFF would only include the 2026 renewal in the final dataset. Out of the 305 preprints included in this analysis, 24 (totaling $8.8 billion in federal spending) ended in calendar year 2024.
A small number of SDP preprints were excluded due to file formatting or data validity issues. Specifically:
- Data from five preprints were encoded differently, so the data could not be programmatically extracted into the dataset and were therefore excluded from the analysis (two from New Hampshire, one from Ohio, and two from Florida, totaling $89 million in federal spending for one year).
- Data from preprints that had obvious data quality issues were excluded from this sample. For instance, two were from Illinois (which projected total annual spending of more than $100 billion) while one from Minnesota did not report spending data in the preprint.
KFF also reviewed all preprints with end dates prior to July 1, 2025, and excluded preprints for the following reasons:
- The preprint was likely funded from COVID-19 relief dollars (including the increased federal funding for home care from the American Rescue Plan Act) and so was unlikely to still be in place.
- The preprint was likely combined into a different preprint when renewed or was otherwise renamed when renewed.
- The preprint ended in 2024, and online research suggests that the payment was discontinued.
See Table 1 for a list of the inclusion criteria, the counts of preprints after each criterion was applied, and the federal spending for preprints that were retained at each stage.
Calculating total spending on SDPs: This analysis used the states’ projected total, federal, and state spending from the preprint. Most preprints are for a one-year period, but some are for longer or shorter periods. In such cases, KFF adjusted the data to be a one-year equivalent. When preprints were for periods shorter than 12 months, dollars were scaled up (e.g., if the preprint was for 6 months, the spending was multiplied by two) and for preprints that were for periods longer than 12 months, spending was scaled down (e.g., retaining two-thirds of spending if the preprint extended for 18 months).
KFF also manually reviewed the federal spending numbers because some states reported them as percentages and others reported them as dollar amounts. Manual review ensured the Python script had adequately handled the different reporting structures.
Calculating SDP spending by service type: For preprints that made payments for multiple service types (which accounted for $32.6 billion in federal spending), spending was apportioned across service types.
- For SDPs directed to hospital and non-hospital services, 90% of spending was allocated to hospital services. Remaining dollars were apportioned equally among any other service types.
- For SDPs directed to both inpatient and outpatient hospital services, 68% of hospital spending was allocated to inpatient services and 32% was allocated to outpatient services. This assumption does not affect the estimates of spending by service type but is relevant for calculating the amount of spending by benchmark rate.
- For SDPs that did not direct any spending to hospital services, spending was allocated equally among named services.
Apportioning spending across service types is difficult, and KFF used a variety of sources to approach developing the most realistic assumptions feasible. KFF analyzed data on Medicaid spending including CMS-64 spending by service type, data on Medicaid spending by service type from the National Health Expenditures, the Congressional Budget Office Medicaid baseline, and existing studies on hospital payment policies such as those from the Medicaid and CHIP Payment and Access Commission (MACPAC). All of those data points suggest that the vast majority of SDP spending pays for hospital services, and $53.1 billion of the $60.5 billion in federal spending from preprints directed to a single provider type went to hospital services. KFF also strove to use an assumption that resulted in estimates of hospital SDP spending that are similar to what could be expected on the basis of other data and research as described above.
When identifying the service types in the preprints, the Python script attempted to align service types between preprint Table 2 (which specifies payment rates for sets of providers) and preprint Question 20 (a checklist of services included in the SDP). In many cases, this alignment involved some uncertainty, requiring manual review and classification of service types.
Identifying benchmarks for MCO payments: The most common type of SDP requires MCOs to make payments that are on top of the regular base payment rate (as opposed to limiting or replacing the negotiated rate). In such cases, payments are measured using a “benchmark” or standardized rate to compare the MCO rates to other payment rates such as those of Medicaid FFS, Medicare FFS, or the average among commercial payers (“average commercial rates”). Among the 305 preprints in this sample (accounting for $93.1 billion in federal spending), 264 preprints are required to report a benchmark (accounting for $87.9 billion in federal spending). KFF used the Python script to identify the applicable benchmark type from the preprint, but also manually reviewed the data since states sometimes used inconsistent terminology to report the same benchmarks.
Identifying payment levels: To identify how current payment rates align with the new limits on SDPs in the reconciliation law, KFF first needed to identify payment levels in the preprints. The level is specified as a percentage of the benchmark (e.g., 90% of average commercial rates or 140% of Medicare rates). Both types of payments were pulled from Table 2 when available. Payment rates for inpatient and outpatient hospital services were tracked separately with each row in Table 2 when applicable.
SDPs for nursing facility services: KFF further limited the sample of SDPs to only those that specified nursing facility services as a service type in Question 20.
Methods Table 1
| Analysis Step | Count of Preprints | Federal Spending Among Preprints (billion $) | Notes |
| Preprints listed on CMS’s website as of May 12, 2026 | 1,038 |
|
|
| All preprints pulled from CMS website | 987 | 246.4 | Some links are broken or duplicates |
| Preprints in time period and states | 570 | 166.1 | Includes the most recent preprint for each state directed payment (SDP) from January 2024 onwards for the 50 states and DC |
| Most recent SDP submission or renewal | 358 | 99.6 |
|
| Preprints without data quality issues | 352 | 99.6 | KFF dropped preprints that were missing information about the start date, end date, spending amounts, etc. |
| Preprints manually reviewed and dropped | 305 | 93.1 | KFF dropped preprints from older years that were subsumed into newer preprints and those that were temporary policies started during the COVID-19 pandemic |
| Include nursing home services | 20 | 2.2 |
|