Medicare

Medicare Open Enrollment

NEW AND NOTEWORTHY

Decoding Medicare Advantage Coding Intensity

Federal payments to Medicare Advantage plans, and adjustments for health status, have come under increased scrutiny. This brief answers key questions about coding intensity, recent steps taken by CMS, the effects on beneficiaries, and other proposals to improve payment accuracy.

Data Visualization

The Facts About Medicare Spending

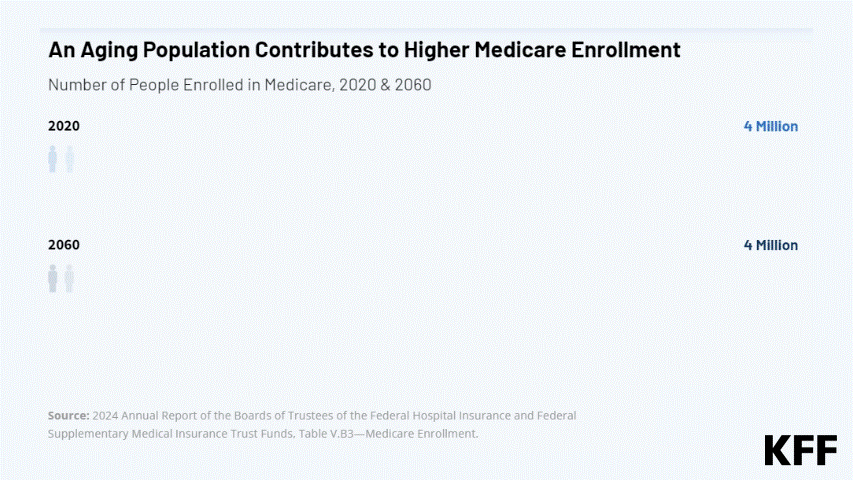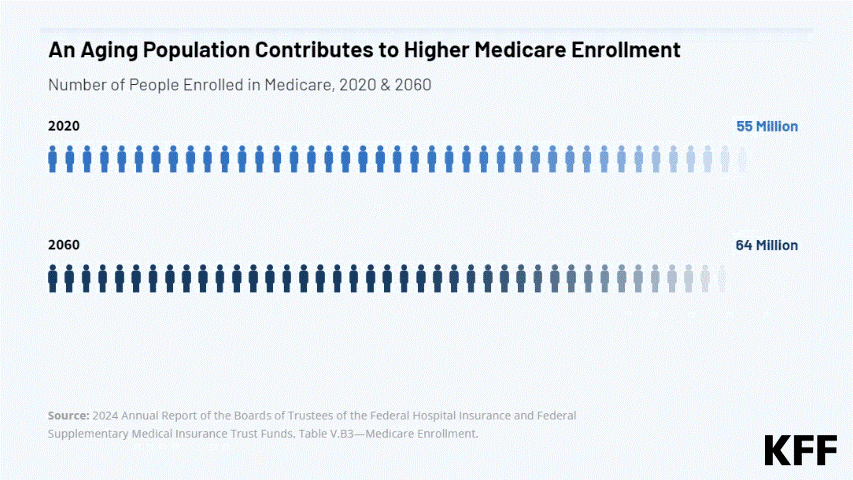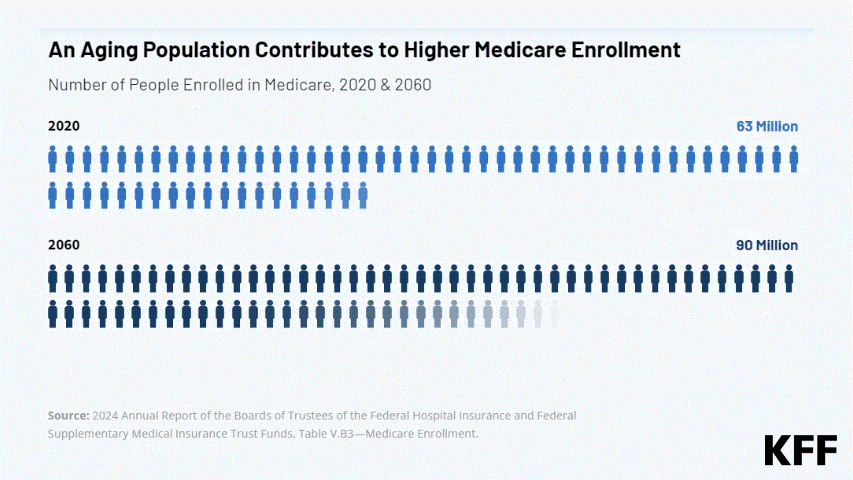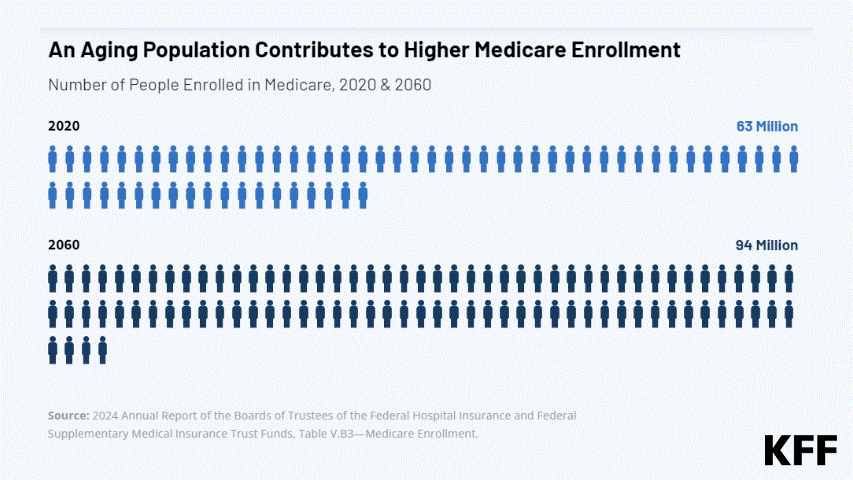
This interactive provides the facts on Medicare spending. Medicare, which serves 67 million people and accounts for 12 percent of the federal budget and 21 percent of national health spending, is often the focus of discussions about health expenditures, health care affordability and the sustainability of federal health programs. Explore data on enrollment growth, Medicare spending trends overall and per person, growth in Medicare spending relative to private insurance, spending on benefits and Medicare Advantage, Part A trust fund solvency challenges, and growth in out-of-pocket spending by beneficiaries.

Read More

Stay informed.

Stay informed.

Filter

1,541-1,550 of 1,622 results

  • Compare Medicare-for-all and Public Plan Proposals

    Interactive

    This side-by-side interactive compares 10 bills to expand public health coverage through Medicare-for-All, a public option and other approaches, that have been introduced in the current Congress. The interactive allows users to compare these proposals across a number of dimensions, including eligibility, benefits, cost sharing, provider payments, and more.

  • Independent Payment Advisory Board (IPAB) Process: A Timeline

    Feature

    IPAB Timeline Download Source Kaiser Family Foundation, “The Independent Payment Advisory Board: A New Approach to Controlling Medicare Spending,” 2011, https://www.kff.org/health-reform/issue-brief/the-independent-payment-advisory-board-a-new/.

  • Modifying Medicare’s Benefit Design: What’s the Impact on Beneficiaries and Spending?

    Report

    This report examines an approach to reforming Medicare that has been a focus of Congressional hearings and featured in several broader debt reduction and entitlement reform proposals, and was included in the June 2016 House Republican health plan. The analysis models four different options for modifying Medicare's benefit design, all of which include a single deductible, modified cost-sharing requirements, a new cost-sharing limit, and a prohibition on first-dollar Medigap coverage. The analysis models the expected…

  • Modifying Traditional Medicare’s Benefit Design Could Reduce Federal Spending But With Cost Tradeoffs Between Beneficiaries and The Federal Government

    News Release

    Revamping traditional Medicare’s benefit design and restricting “first-dollar” supplemental coverage could reduce federal spending, simplify cost sharing, protect against high medical costs, decrease out-of-pocket spending for many beneficiaries, and provide more help to those with low incomes -- but would be unlikely to achieve all of these goals simultaneously.

  • Analysis Finds End-of-Life Medicare Spending Declines With Age Among Seniors

    News Release

    Among beneficiaries who died in 2014, Medicare spent significantly more per person on medical services for seniors in their late sixties and early seventies than on older beneficiaries, according to a new data note from the Kaiser Family Foundation. The analysis comes at a time when physicians can now be reimbursed by Medicare for end-of-life care discussions with their patients. The analysis of Medicare claims data through 2014 finds that among those who died in…

  • Turning Medicare Into a Premium Support System: Frequently Asked Questions

    Issue Brief

    Premium support is a general term used to describe an approach to reform Medicare that aims to reduce the growth in Medicare spending. These FAQs raise and discuss basic questions about the possible effects of a premium support system for Medicare beneficiaries, the federal budget, health care providers, and private health plans.

  • Medicare’s Role for People Under Age 65 with Disabilities

    Issue Brief

    This issue brief examines the role of Medicare for people under age 65 with disabilities, including how this group qualifies for Medicare, the characteristics of people under age 65 with disabilities compared to those age 65 or older, and how sources of supplemental coverage and prescription drug coverage, spending and use of services, and access to care differ for Medicare beneficiaries under age 65 with disabilities and older beneficiaries.

  • KFF Analysis: Number of Coronavirus Cases, Distribution of $30B in CARES Act funding and Medicare Advantage Penetration by State

    Fact Sheet

    Number of Coronavirus Cases, Distribution of $30B in CARES Act funding and Medicare Advantage Penetration by StateStateNumber ofCOVID-19 Cases on April 21, 2020Percent of Total COVID-19 CasesFirst Distribution of CARES Act PaymentsPercent of Total Money DistributedPercent of Medicare Beneficiaries in Medicare Advantage, 2020New York253,400.0032.1%$1,859,574,4346.2%40%New Jersey88,806.0011.3%$919,426,8013.1%29%Massachusetts39,643.005.0%$841,425,1202.8%23%Pennsylvania34,005.004.3%$1,246,250,0764.2%41%California33,866.004.3%$2,920,960,7339.7%40%Michigan32,000.004.1%$936,700,1393.1%42%Illinois31,508.004.0%$1,204,103,1804.0%25%Florida27,058.003.4%$2,220,563,1377.4%43%Louisiana24,523.003.1%$474,891,7351.6%38%Connecticut19,815.002.5%$377,981,2571.3%41%Texas20,087.002.5%$2,089,066,4527.0%37%Georgia19,398.002.5%$792,069,1602.6%37%Maryland14,193.001.8%$742,225,3062.5%11%Ohio12,919.001.6%$989,773,4173.3%39%Washington12,486.001.6%$553,838,8061.8%33%Indiana11,688.001.5%$668,604,6142.2%32%Colorado10,112.001.3%$360,905,4821.2%38%Virginia9,097.001.2%$814,360,4672.7%21%Tennessee7,238.000.9%$739,723,3472.5%38%North Carolina6,979.000.9%$919,171,0873.1%36%Missouri5,963.000.8%$618,601,1672.1%35%Rhode Island5,090.000.6%$90,459,8340.3%39%Arizona5,068.000.6%$707,587,4822.4%39%Alabama5,092.000.6%$449,481,9451.5%41%Mississippi4,512.000.6%$374,847,7901.2%20%Wisconsin4,541.000.6%$471,681,0771.6%42%South Carolina4,439.000.6%$518,022,4631.7%28%Nevada3,830.000.5%$241,471,8410.8%36%Utah3,213.000.4%$185,292,4220.6%36%Iowa3,159.000.4%$297,929,1711.0%22%Kentucky3,050.000.4%$452,761,1711.5%34%District of Columbia3,098.000.4%$84,989,0990.3%20%Delaware2,745.000.3%$154,114,1180.5%17%Oklahoma2,680.000.3%$489,853,9981.6%22%Minnesota2,470.000.3%$472,206,1221.6%43%Kansas2,070.000.3%$325,135,9501.1%19%Oregon1,956.000.2%$291,029,0251.0%42%Arkansas1,990.000.3%$326,536,0431.1%26%New Mexico1,971.000.2%$169,486,1320.6%35%South Dakota1,685.000.2%$107,650,2010.4%19%Idaho1,736.000.2%$135,028,0560.5%33%Nebraska1,648.000.2%$225,027,9120.8%17%New Hampshire1,447.000.2%$164,580,3860.5%19%Puerto Rico1,298.000.2%$41,889,8220.1%70%West Virginia908.000.1%$246,574,8510.8%31%Maine875.000.1%$145,763,8120.5%36%Vermont816.000.1%$54,457,8700.2%12%North Dakota627.000.1%$91,064,5790.3%17%Hawaii584.000.1%$132,536,0760.4%44%Montana433.000.1%$111,503,2480.4%18%Alaska321.000.0%$71,248,1230.2%1%Wyoming429.000.1%$66,393,1630.2%3%NOTES: COVID-19 data as of 4/21/2020 at 10:38 AM.SOURCES: Johns Hopkins University, [Coronavirus COVID-19 Global Cases by the Center for…