
1115 Waiver Watch: A Look at Budget Neutrality Policy Changes
Section 1115 Medicaid demonstration waivers offer states an avenue to test new approaches in Medicaid that differ from what is required by federal statute, if [in the Health and Human Services (HHS) Secretary’s view] the approach is likely to “promote the objectives of the Medicaid program.” Nearly all states have at least one active Section 1115 waiver and some states have multiple 1115 waivers. Under long-standing policy and practice, Section 1115 demonstration waivers were required to be “budget neutral” to the federal government over the course of the waiver, meaning federal costs under the waiver could not exceed what they would have been for the state without the waiver. Using 1115 waivers has allowed states to generate “savings” that can be reinvested (under the waiver) to support new initiatives (e.g. coverage expansions, new benefits etc.).
The 2025 reconciliation law, signed by President Trump on July 4, 2025, codified budget neutrality in federal statute (for the first time) and added a requirement that the Centers for Medicare and Medicaid Services (CMS) Chief Actuary certify 1115 waivers are budget neutral before approval. In June 2026, CMS released initial guidance on CMS’ interpretation of the new statutory provision and updated budget neutrality policy guidance that will be implemented through forthcoming rulemaking (expected in early 2027). Overall, the new guidance makes significant changes to how CMS will assess budget neutrality and may reduce state flexibility to pursue certain 1115 initiatives. This policy guidance follows administrative action to phase out or rescind certain Biden-era waiver policies (related to health-related social needs services (HRSN), continuous eligibility policies, workforce initiatives, and certain waiver financing tools).
In August 2026, Arkansas announced that CMS will not be approving the state’s request to renew its “ARHOME” waiver (set to expire at the end of 2026) due to the new budget neutrality rules. Under the waiver, Arkansas enrolled its Medicaid expansion population directly into ACA Marketplace plans. The state is seeking a temporary two-year extension to provide time to develop a new solution (delivery system) and transition plan. In addition, while additional guidance will be forthcoming (including clarification on how states may be able to fund infrastructure costs under new budget neutrality rules), CMS approved five state waivers that support community reentry for people who are incarcerated in late September 2026 (D.C., Louisiana, Maine, Minnesota, and Nevada).
This brief discusses key policy changes included in the June 2026 CMS budget neutrality guidance and identifies open questions involving how the policy changes may be further clarified in the forthcoming rule and how the changes may impact states with existing 1115 waivers or states interested in applying for new demonstration waivers.
Key takeaways include:
- The new guidance outlines major shifts in policy and aims to reduce federal 1115 waiver expenditures. Key changes include a more rigorous prospective determination of budget neutrality, new rules involving “hypothetical” expenditures that may require states to demonstrate “savings” for more initiatives, the inclusion of administrative costs in budget neutrality calculations, and limits to budget neutrality savings.
- Forthcoming rules (expected in early 2027) may include further guidance and clarification for states. Key areas where additional clarification and information may be needed include financial impact analysis methodology expectations, monitoring requirements, evaluation and renewal standards, and financial risk clarification.
- CMS’s response to waivers up for renewal (in 2026 and early 2027) may provide insights involving how the new rules will be applied and how states may adapt to changing policies. States may have difficulty gaining approval for HRSN services, delivery system reforms, certain “home- and community-based services” (HCBS) 1115 initiatives, and/or uncompensated care pool financing under the new rule, if these services or initiatives newly require offsetting savings or states are constrained by new rules involving the accrual and rollover of waiver “savings.”
How has waiver budget neutrality historically been assessed?
Under long-standing policy and practice, Section 1115 waivers were required to be “budget neutral” to the federal government over the course of the waiver (usually 5 years). Section 1115 waiver budget neutrality meant that federal spending under a waiver could not exceed the projected costs without the waiver. Budget neutrality calculations and the use of any budget neutrality “savings” have been negotiated between states, CMS, and the Office of Management and Budget (OMB). At a high level, the budget neutrality process has included the following:
- Setting expenditure limits. A “without waiver” baseline was established (when a waiver was approved by CMS) that acted as a limit on total demonstration spending. Typically, budget neutrality calculations were determined on a per enrollee basis, putting states at risk for the costs per individual but not for the number of individuals enrolled.
- Excluding hypothetical expenditures. Costs for some populations and/or services, referred to as “hypothetical,” were excluded from budget neutrality calculations if they were similar to populations or services that could have been covered without the 1115 waiver, generally meaning states did not need offsetting savings to pay for these expenditures.1
- Assessing budget neutrality, including identifying savings. While the “without waiver” baseline was compared to projected “with waiver” spending (using state data to generate aggregate spending projections) prior to approval, budget neutrality was formally assessed at the end of the demonstration period. If a state exceeded the “without waiver” limit, it was required to pay back any federal spending above the limit. If demonstration spending was below the limit, a state accumulated budget neutrality “savings” that could be used to fund the federal share of costs not otherwise allowed (in future demonstrations).
Because Section 1115 budget neutrality has not been defined in federal statute or regulations, CMS agency policy and guidance to states has changed over time. For example, the first Trump administration made changes to 1115 waiver budget neutrality policy in 2018 (e.g. changing the rules for calculating the “without waiver” baseline) that limited the amount of federal funds that could be used for waiver spending. The Biden administration later made changes that aimed to provide greater flexibility for states to design and implement 1115 demonstration programs, including health-related social needs (HRSN) initiatives.
The U.S. Government Accountability Office (GAO) has raised concerns involving CMS’s budget neutrality policy. Specifically,GAO has raised concerns related to transparency and accountability in the 1115 waiver approval process, the methods used to calculate spending baselines (“with” and “without” waiver) and waiver “savings,” and the monitoring of federal spending under 1115 waivers. Most recently, a 2025 GAO report raised concerns about HRSN services and reentry services, approved under 1115 waiver authority as “hypothetical” expenditures (that do not require offsetting savings). After the 2025 GAO report was released, the Republican Chairman of the House Committee on Energy and Commerce called for “stronger oversight” of 1115 waiver demonstrations.
What budget neutrality changes will go into effect in January 2027?
In June 2026, CMS released initial guidance outlining a new approach to budget neutrality policy that will be effective January 1, 2027. The 2025 reconciliation law codified budget neutrality in federal statute for the first time and added a requirement that the CMS Chief Actuary certify 1115 waivers are budget neutral prior to approval. The new guidance indicates states will need to perform an “actuarial, economic, statistical, or other comparable rigorous analysis of the projected financial impacts of individual demonstration activities” before a waiver can be approved. In the guidance, CMS says it aims to reduce state reliance on Section 1115 authority, directing states to use alternative authorities (e.g. state plan authority, 1915 authority) where possible. While budget neutrality policy changes will be implemented formally through CMS rulemaking (expected in early 2027), the new policies described in the guidance letter will take effect on January 1, 2027, even if a final rule is not released by then.
The new guidance outlines major shifts in policy, beyond the codification of the longstanding budget neutrality policy, and aims to reduce federal 1115 waiver expenditures. Key changes to budget neutrality policy described in the June 2026 guidance letter are included below:
- Replacing expenditure limits assessed at the end of the demonstration with a more rigorous prospective analysis of financial impacts. Instead of setting expenditure limits (based on state data/aggregate projections) and formally assessing budget neutrality after the demonstration period ends, the CMS Chief Actuary will determine whether a demonstration is budget neutral (and approvable) at application based on an actuarial, economic, or statistical analysis of projected financial impacts of individual demonstration activities. These rigorous prospective analyses may limit waiver approvals. Activities will be classified as either “1115-only” (subject to budget neutrality calculations) or “Medicaid Authorizable Populations and Services” (or “MAPS”) (considered to have a net financial impact of zero, because they are activities the state could have implemented through state plan or other authority).
- New rules for “hypothetical” expenditures. The guidance replaces the concept of “hypothetical” expenditures with a new “Medicaid Authorizable Populations and Services” (“MAPS”) policy. Under the new “MAPS” policy, to be excluded from the budget neutrality calculation, both the service and the population receiving the service must be coverable under a different Medicaid authority. This stricter standard may result in the recategorization of certain activities currently considered “hypothetical” (e.g. some home- and community-based services (HCBS), HRSN, infrastructure costs) as “1115-only,” which will require states to find savings offsets.2
- Inclusion of administrative costs. Budget neutrality calculations will consider the administrative costs associated with the activity, which have historically been excluded.
- Limits to budget neutrality savings. Under the new approach, savings may be more difficult to generate, and rollover savings will be limited. Currently, states can accrue savings if their actual spending stays below the projected (“without waiver”) spending baseline and may use the savings for multiple future demonstration periods. Under the new approach, savings will be tied to actuarial determinations of savings potential and may only be used in the period they are accrued or the demonstration period that immediately follows. In its June 2026 slide deck, CMS indicated managed care will not be able to generate budget neutrality savings. (States have used savings from Medicaid managed care in the past to offset other waiver costs.)
Obtaining approval for Section 1115 waivers takes time—new requirements add complexity and may further lengthen the approval process. There has been significant variation in the length of time it takes to get final approval of a waiver. NAMD has noted the typical negotiation/approval timeframe ranges from 6 months to 2 years. Under new requirements, states will need to conduct rigorous analyses of expected cost impacts and provide significant implementation details prior to approval (currently, states often submit these implementation details and protocols after gaining approval). Due to these budget neutrality policy changes, CMS recently rescinded guidance allowing certain renewals to be done via a “fast-track” process. The fast-track process was introduced in 2015, offering states requesting straightforward renewals (i.e. with few to no changes) a standard template and expedited review/approval time (often used for less complex / narrow waivers, like family planning-only waivers).
What are key 1115 areas to watch for clarification or additional guidance?
The June 2026 guidance indicates CMS intends to formally implement budget neutrality policy changes through rulemaking (although the new policies will take effect on January 1, 2027, even if a final rule is not released by then).
Key areas to watch for additional clarification in the proposed rule include:
- Financial impact analysis methodology. While CMS notes it will give states flexibility to determine the form of analysis used to estimate/project financial impacts of demonstration activities (e.g. actuarial, statistical, economic), additional clarification involving the standards the Chief Actuary will use to evaluate financial impacts is likely needed. States may also need additional guidance on how to estimate/project waiver-specific administrative costs, as well as the expected standards for determining indirect impacts and utilization shifts at the activity level.
- Monitoring information. In its June 2026 guidance, CMS noted states would be expected to monitor key indicators (e.g. program outcomes and expenditures) and to manage demonstrations within “to be defined” CMS guardrails. States would need to complete “corrective actions” if expenditures deviate “substantially” from initial projections. It remains unclear how CMS will define “substantial” deviations or what types of corrective actions may be imposed.
- Evaluation and renewal standards. CMS intends to propose revised evaluation expectations for demonstrations that are meeting evaluation goals, to ensure “sustained achievement in outcomes.”
- Financial risk clarification. The current guidance also notes that while analysis should generally be done on a per-member per-month basis, enrollee count estimates should also be included to generate aggregate impacts. The new rule may also provide clarity on whether (and when) states would be exposed to financial risk if they experience enrollment or utilization shifts beyond projected levels.
CMS’s budget neutrality and related waiver policies are likely to reduce state flexibility to pursue 1115 waivers generally and certain initiatives specifically. Specifically, states may have difficulty gaining approval for HRSN services, delivery system reforms, certain HCBS initiatives, and/or uncompensated care pool financing under the new rules, if these services or initiatives require offsetting savings (that were not previously required) or states are constrained by new rules involving the accrual and rollover of waiver “savings.” Once an activity is labeled “1115-only,” the state must prove net savings to pay for it. Finding savings to “pay for” these services may be harder, as CMS is limiting rollovers and including administrative costs in the budget neutrality calculation. Additionally, certain programs currently “deemed budget neutral,” like coverage of traditional healing practices (for American Indian and Alaska Native people), would need to be classified as “MAPS” or 1115-only activities, which may require states to offset those costs (if determined 1115-only). While CMS recently approved two new traditional healing waivers (Maine and Utah), it did not indicate how these waivers would be treated in the future under the new budget neutrality rules. CMS has already indicated that it will not approve Arkansas’s request to renew its “ARHOME” waiver under new budget neutrality rules (which provides coverage to Medicaid expansion adults through Marketplace plans). The state is seeking a temporary two-year extension to develop a new delivery system.
Many states have obtained approval for IMD (Institutions for Mental Disease) services and/or reentry services under 1115 authority, which will not require cost offsets under the new guidance. The new guidance specifies that expenditures that could be made under state plan or other authority but for the site of service (e.g. IMDs, in carceral settings) will be considered “MAPS” expenditures that would not require offsets. However, infrastructure funds used to support the implementation of reentry waivers will no longer be considered “hypothetical” (or “MAPS”). (CMS notes additional reentry guidance is forthcoming.) The Trump administration recently approved five new state reentry waivers; in these approvals, CMS indicated it does not anticipate approving infrastructure expenditures and will instead work with states on potential pathways for administrative claiming to support implementation cost.
Future waiver activity, including CMS approvals and state requests, will provide greater insight into how the new budget neutrality rules will be applied and how states may adapt to changing federal 1115 priorities and budget neutrality policy.
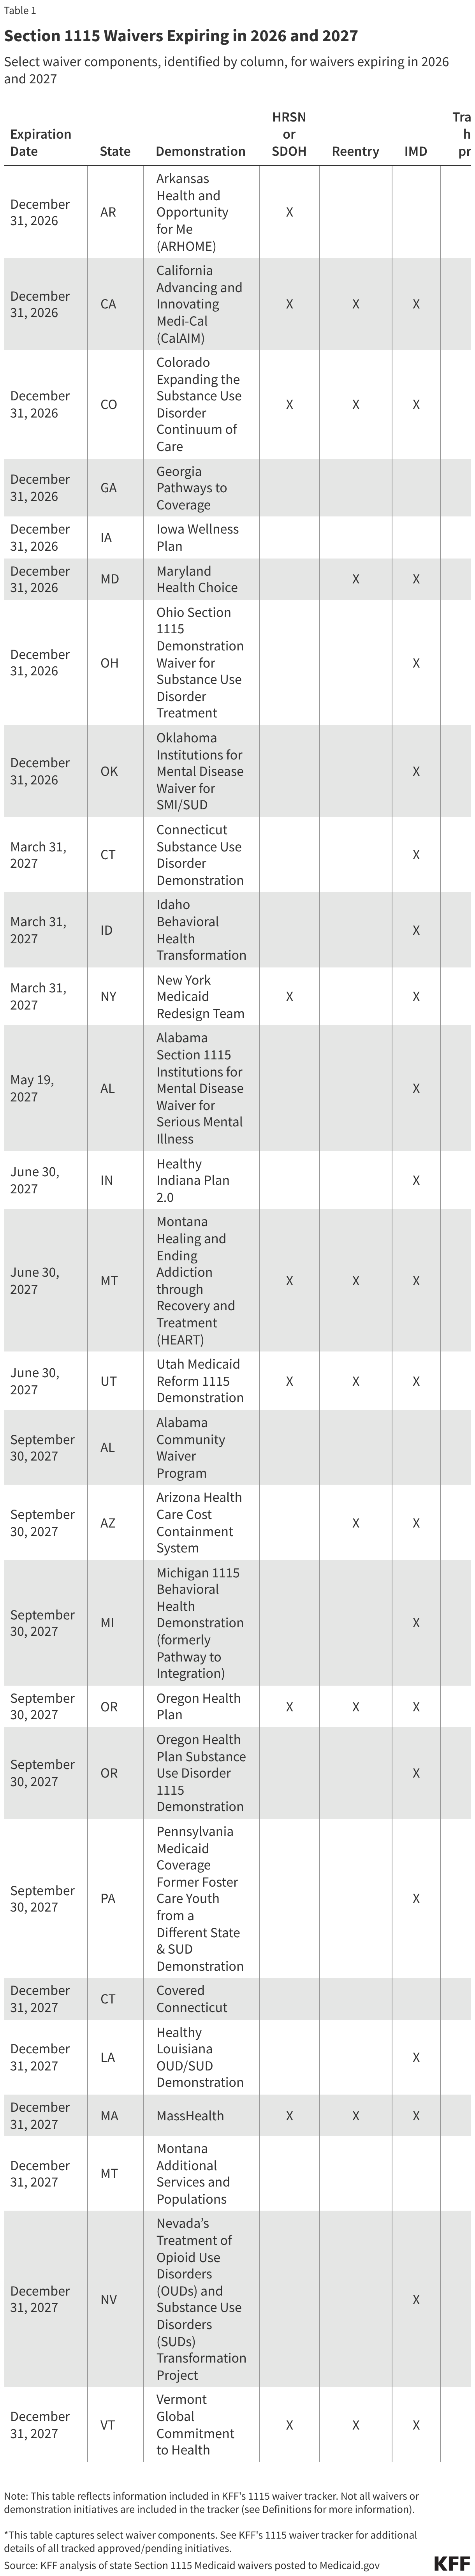
- Waivers expiring in 2026 & 2027 (Table 1). States with waivers expiring soon (27 waivers are due to expire by the end of 2027) may have already started the renewal process or submitted requests to CMS (that are currently pending) and may need to make changes based on the new budget neutrality policy. For some states with waivers expiring before the end of the year, CMS may choose to approve certain demonstration activities under the current methodology, while continuing negotiation of other requests into 2027 when new rules apply.3
- Amendment requests for ongoing waivers. The guidance indicates mid-demonstration amendment requests would trigger full waiver review using the new budget neutrality rules and require certification from the Chief Actuary. This requirement may make states with waiver expiration dates further out reticent to pursue mid-demonstration amendments or reconsider currently pending amendment requests.
- Transition initiatives to other Medicaid authorities. States may choose to transition provisions currently authorized under 1115 to State Plan or other federal Medicaid authorities. This may have implications for states, including finding the administrative capacity to reorganize longstanding programs—at a time state resources are particularly stretched, implementing the 2025 reconciliation law provisions.
- Although hypothetical expenditures were usually subject to separate spending limits / caps. ↩︎
- In addition, certain 1115 expenditures (e.g. traditional health care practices, out-of-state former foster care youth coverage) that were previously “deemed” budget neutral now must be classified (as “MAPS” or “1115-only”), which may require states to offset those costs with savings if they are determined to be “1115-only.” ↩︎
- For example, in recent renewal approvals in D.C. and Maine, CMS approved reentry demonstrations but said it would continue to work with the states on the details of pending SDOH requests. ↩︎